Molecular Mechanisms of Transfusion-Associated Immunomodulation and Its Impact in the Critically Ill


Abstract
1. Introduction
2. Methods
3. Results
3.1. Molecular Mechanisms of Transfusion-Associated Immunomodulation
3.2. Hemolysis Byproducts
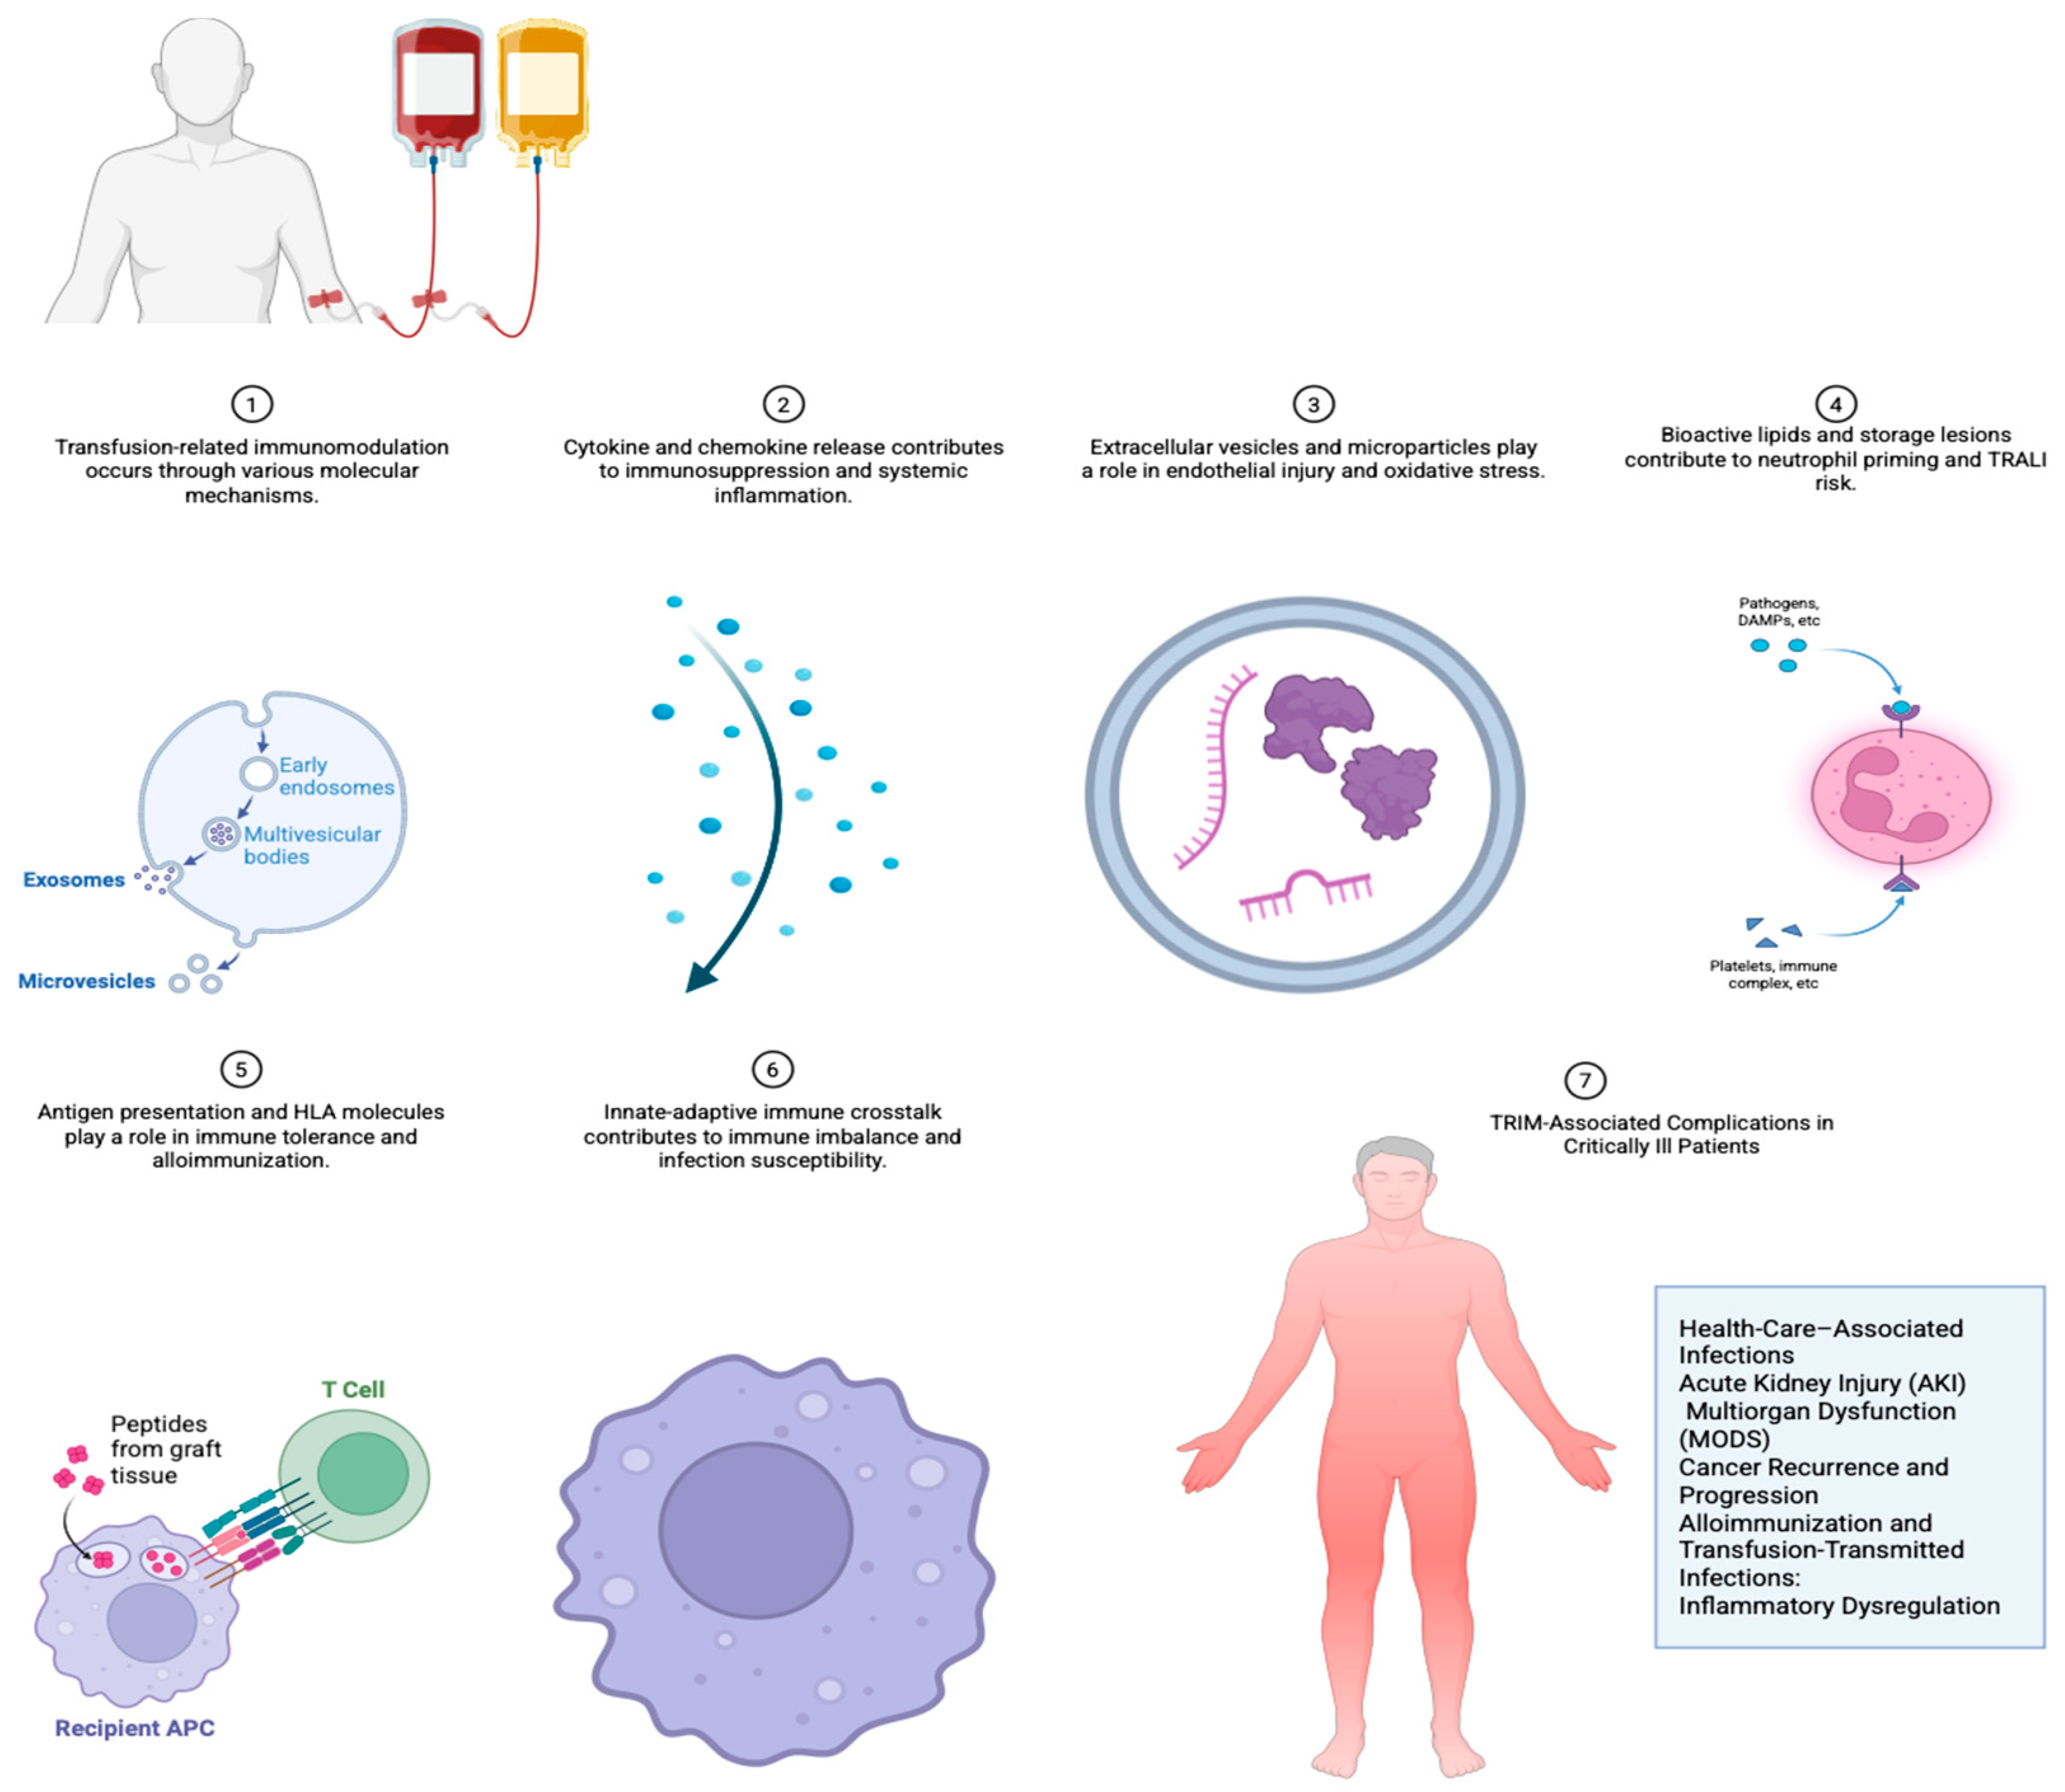
3.3. Pathophysiology of TRIM-Associated Complications in Critically Ill Patients
- (A)
- Health-Care–Associated Infections (HCAI): Transfused allogeneic leukocytes and soluble mediators suppress innate and adaptive immune function, primarily by inhibiting natural killer (NK) cell cytotoxicity and expanding regulatory T cells (Tregs). Cytokines such as IL-10 and TGF-β, present in stored blood products, further downregulate proinflammatory pathways, impairing pathogen clearance. This state of relative immunosuppression predisposes critically ill patients, who are already vulnerable to systemic inflammation, to pneumonia, bloodstream infections, and sepsis [41,42,43,44,45].
- (B)
- Pulmonary Complications: TRALI and Acute Lung Injury (ALI): The pathogenesis of TRALI is an example of the “two-hit” hypothesis [45]. In critically ill patients, the first hit is systemic inflammation caused by sepsis, trauma, or surgery, which primes pulmonary neutrophils and endothelial cells [46]. The second hit comes from transfused mediators such as anti-leukocyte antibodies, bioactive lipids, and extracellular vesicles, that activate primed neutrophils within the pulmonary microvasculature. This triggers capillary leak, oxidative damage, and an inflammatory cascade that culminates in acute lung injury or Acute Respiratory Distress Syndrome (ARDS) like syndromes [47,48,49,50,51,52].
- (C)
- Acute Kidney Injury (AKI) and Multiorgan Dysfunction (MODS): Renal injury secondary to TRIM is caused by oxidative stress, alteration in the microcirculatory flow, and systemic inflammation [53,54]. Bioactive lipids and microparticles promote endothelial dysfunction, cause, disrupt renal perfusion, and contribute to tubular injury [55]. Additionally, cytokine imbalance propagates systemic immune dysregulation, extending the effect to multiple organs and amplifying the risk of MODS [56].
- (D)
- Increased Length of Stay and Mortality: The combination of infection risk, pulmonary complications, and organ dysfunction directly translates into prolonged ICU and hospital stays [57]. Immunological derangements induced by transfusion impair the recovery from acute illness, and excessive inflammation contributes to complications. Although the impact on mortality remains inconsistent across trials, observational evidence has shown that cumulative transfusion correlates with worse survival, likely mediated by these pathophysiological pathways [58].
- (E)
- Cancer Recurrence and Progression: In surgical oncology patients requiring intensive care, donor-derived leukocytes, HLA, and cytokines suppress cytotoxic T-cell and NK cell activity and promote regulatory pathways that favor tumor immune escape. This mechanism explains the association between perioperative transfusion and increased recurrence or metastasis in colorectal, urologic, and other solid tumors [34,37,59,60,61].
- (F)
- Alloimmunization and Transfusion-Transmitted Infections: Alloimmunization occurs when the recipient’s immune system creates antibodies against foreign antigens from a donor, caused by the interaction between donor leukocytes and the recipient’s HLA [62]. Leukoreduction systems, which filter out white blood cells, effectively reduce this risk, but do not eliminate it because a small number of leukocytes and other foreign antigens can still be present [62]. Transfusion-transmitted infections (TTIs) can also occur, though leukoreduction has been shown to significantly decrease the incidence of TTIs like bacterial sepsis. Removing donor leukocytes and reducing the accumulation of cytokines during storage, leukoreduction decreases the potential for immune tolerance, alloimmunization, and infectious complications [63,64]. Although its impact on mortality has not been definitively proven, the biological plausibility and the consistent infection signals support its widespread use. Pre-storage leukoreduction is superior to post-storage approaches; timing of the intervention is critical [65,66,67,68]. Transfusion-transmitted cytomegalovirus (CMV) remains a concern in immunocompromised critically ill patients, as TRIM-related immunosuppression also enhances viral replication and impairs host defense [69,70,71,72,73].
- (G)
- Inflammatory Dysregulation and the “Two Hit” Model: The most unifying feature of TRIM in the critically ill is its capacity to exacerbate preexisting inflammation [74]. In patients with trauma or sepsis, the immune system and its interaction with the endothelial cells are already activated; transfusion provides a secondary insult through extracellular vesicles, oxidized lipids, and cytokine accumulation [75]. The two-hit model explain how transfusion precipitates immune dysregulation and clinical complications. This model posits that an initial insult (1st hit) or pre-existing inflammatory state in the recipient primes the immune system, making it susceptible to a “second hit” from transfused blood products [74]. This secondary insult, (2nd Hit), mediated by biologically active components, exacerbate systemic inflammation or induce immunosuppression, leading to adverse clinical outcomes [74,75]. This dual-trigger mechanism reconciles the contradictory observations observed after transfusion, both immunosuppressive effects, and detrimental outcomes, such as increased infection rates and tumor recurrence [76].
4. Plasma, Platelet, and Cryoprecipitate Mechanisms of TRIM
5. Cell-Type–Specific Mechanisms Underlying TRIM
6. Research Frontiers
7. Conclusions
Author Contributions
Funding
Data Availability Statement
Acknowledgments
Conflicts of Interest
Abbreviations
| APC | Antigen-presenting cell |
| ATP | Adenosine triphosphate |
| CD40L | Cluster of differentiation 40 ligand |
| EVs | Extracellular vesicles |
| HLA | Human leukocyte antigen |
| HO-1 | Heme oxygenase-1 |
| IL | Interleukin |
| MHC | Major histocompatibility complex |
| mtDNA | Mitochondrial DNA |
| NO | Nitric oxide |
| PAMPs | Pathogen-associated molecular patterns |
| RBCs | Red blood cells |
| ROS | Reactive oxygen species |
| sCD40L | Soluble CD40 ligand |
| TH2 | T helper 2 cells |
| TRALI | Transfusion-related acute lung injury |
| TRIM | Transfusion-associated immunomodulation |
| WBCs | White blood cells |
References
- Youssef, L.A.; Spitalnik, S.L. Transfusion-related immunomodulation: A reappraisal. Curr. Opin. Hematol. 2017, 24, 551–557. [Google Scholar] [CrossRef] [Scilit]
- Yoshida, T.; Prudent, M.; D’Alessandro, A. Red blood cell storage lesion: Causes and potential clinical consequences. Blood Transfus. 2019, 17, 27–52. [Google Scholar] [CrossRef] [Scilit]
- D’Alessandro, A.; Zimring, J.C. From metabolomics to transfusion-associated immunomodulation. Curr. Opin. Immunol. 2025, 96, 102646. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marcoux, G.; Hasse, S.; Olsson, M.L.; Egesten, A.; Duchez, A.C. Extracellular vesicle impact on immunity following blood transfusion. Curr. Opin. Immunol. 2025, 95, 102603. [Google Scholar] [CrossRef] [Scilit]
- Remy, K.E.; Hall, M.W.; Cholette, J.; Juffermans, N.P.; Nicol, K.; Doctor, A.; Blumberg, N.; Spinella, P.C.; Norris, P.J.; Dahmer, M.K.; et al. Pediatric Critical Care Blood Research Network (Blood Net). Mechanisms of red blood cell transfusion-related immunomodulation. Transfusion 2018, 58, 804–815. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dimitrov, J.D.; Roumenina, L.T.; Perrella, G.; Rayes, J. Basic Mechanisms of Hemolysis-Associated Thrombo-Inflammation and Immune Dysregulation. Arterioscler. Thromb. Vasc. Biol. 2023, 43, 1349–1361. [Google Scholar] [CrossRef] [Scilit]
- Olonisakin, T.F.; Suber, T.; Gonzalez-Ferrer, S.; Xiong, Z.; Peñaloza, H.F.; van der Geest, R.; Xiong, Y.; Osei-Hwedieh, D.O.; Tejero, J.; Rosengart, M.R.; et al. Stressed erythrophagocytosis induces immunosuppression during sepsis through heme-mediated STAT1 dysregulation. J. Clin. Investig. 2021, 131, e137468. [Google Scholar] [CrossRef] [Scilit]
- Rapido, F.; Brittenham, G.M.; Bandyopadhyay, S.; La Carpia, F.; L’Acqua, C.; McMahon, D.J.; Rebbaa, A.; Wojczyk, B.S.; Netterwald, J.; Wang, H.; et al. Prolonged red cell storage before transfusion increases extravascular hemolysis. J. Clin. Investig. 2017, 127, 375–382. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pandey, S.; Mahato, M.; Srinath, P.; Bhutani, U.; Goap, T.J.; Ravipati, P.; Vemula, P.K. Intermittent scavenging of storage lesion from stored red blood cells by electrospun nanofibrous sheets enhances their quality and shelf-life. Nat. Commun. 2022, 13, 7394. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.S.; Kim-Shapiro, D.B. Stored blood: How old is too old? J. Clin. Investig. 2017, 127, 100–102. [Google Scholar] [CrossRef] [Scilit]
- Baek, J.H.; Yalamanoglu, A.; Gao, Y.; Guenster, R.; Spahn, D.R.; Schaer, D.J.; Buehler, P.W. Iron accelerates hemoglobin oxidation increasing mortality in vascular diseased guinea pigs following transfusion of stored blood. JCI Insight 2017, 2, e93577. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bozza, M.T.; Jeney, V. Pro-inflammatory Actions of Heme and Other Hemoglobin-Derived DAMPs. Front. Immunol. 2020, 11, 1323. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garraud, O.; Tariket, S.; Sut, C.; Haddad, A.; Aloui, C.; Chakroun, T.; Laradi, S.; Cognasse, F. Transfusion as an Inflammation Hit: Knowns and Unknowns. Front. Immunol. 2016, 7, 534. [Google Scholar] [CrossRef] [Scilit]
- Laurén, E.; Sankkila, L.; Pettilä, V.; Kerkelä, E. Immunomodulatory Properties of Packed Red Blood Cells during Storage. Transfus. Med. Hemother. 2022, 50, 208–217. [Google Scholar] [CrossRef] [Scilit]
- Hawwari, I.; Roßnagel, L.; Rosero, N.; Maasewerd, S.; Vasconcelos, M.B.; Jentzsch, M.; Demczuk, A.; Teichmann, L.L.; Meffert, L.; Bertheloot, D.; et al. Platelet transcription factors license the pro-inflammatory cytokine response of human monocytes. EMBO Mol. Med. 2024, 16, 1901. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Silliman, C.C.; Voelkel, N.F.; Allard, J.D.; Elzi, D.J.; Tuder, R.M.; Johnson, J.L.; Ambruso, D.R. Plasma and lipids from stored packed red blood cells cause acute lung injury in an animal model. J. Clin. Investig. 1998, 101, 1458. [Google Scholar] [CrossRef] [Scilit]
- Binnington, B.; Sakac, D.; Yi, Q.; Tong, T.N.; Parmar, N.; Duong, T.T.; Yeung, R.S.M.; Pendergrast, J.; Branch, D.R. Stability of 40 cytokines/chemokines in chronically ill patients under different storage conditions. Cytokine 2020, 130, 155057. [Google Scholar] [CrossRef] [Scilit]
- Ma, S.; Xia, H.; Gong, P.; Yu, Z. Red blood cell-derived extracellular vesicles: An overview of current research progress, challenges, and opportunities. Biomedicines 2023, 11, 2798. [Google Scholar] [CrossRef] [Scilit]
- Hod, E.A.; Spitalnik, S.L. Stored red blood cell transfusions: Iron, inflammation, immunity, and infection. Transfus. Clin. Biol. 2012, 19, 84–89. [Google Scholar] [CrossRef] [Scilit]
- Kristiansson, M.; Soop, M.; Saraste, L.; Sundqvist, K. Cytokines in stored red blood cell concentrates: Promoters of systemic inflammation and simulators of acute transfusion reactions? Acta Anaesthesiol. Scand. 1996, 40, 496. [Google Scholar] [CrossRef] [Scilit]
- Suades, R.; Greco, M.F.; Padró, T.; Badimón, L. Extracellular Vesicles as Drivers of Immunoinflammation in Atherothrombosis. Cells 2022, 11, 1845. [Google Scholar] [CrossRef] [Scilit]
- Ortmann, W.; Such, A.; Cichoń, I.; Baj-Krzyworzeka, M.; Węglarczyk, K.; Kołaczkowska, E. Large extracellular vesicle (EV) and neutrophil extracellular trap (NET) interaction captured in vivo during systemic inflammation. Sci. Rep. 2024, 14, 4680. [Google Scholar] [CrossRef] [Scilit]
- He, Y.; Wu, Q. The Effect of Extracellular Vesicles on Thrombosis. J. Cardiovasc. Transl. Res. 2022, 16, 682. [Google Scholar] [CrossRef] [Scilit]
- Babaev, A.; Pozzi, F.; Hare, G.; Zhang, H. Storage of Red Blood Cells and Transfusion-Related Acute Lung Injury. J. Anesth. Crit. Care 2014, 1, 00002. [Google Scholar] [CrossRef] [Scilit]
- Hariri, G.; Bourcier, S.; Marjanovic, Z.; Joffre, J.; Lemarié, J.; Lavillegrand, J.; Charue, D.; Duflot, T.; Bigé, N.; Baudel, J.L.; et al. Exploring the microvascular impact of red blood cell transfusion in intensive care unit patients. Crit. Care 2019, 23, 292. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rice, T.C.; Pugh, A.M.; Caldwell, C.C.; Schneider, B.S.P. Balance Between the Proinflammatory and Anti-Inflammatory Immune Responses with Blood Transfusion in Sepsis. Crit. Care Nurs. Clin. N. Am. 2017, 29, 331–340. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Green, S.M.; Padula, M.P.; Marks, D.C.; Johnson, L. The Lipid Composition of Platelets and the Impact of Storage: An Overview. Transfus. Med. Rev. 2020, 34, 108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Valkonen, S.; Holopainen, M.; Colas, R.A.; Impola, U.; Dalli, J.; Käkelä, R.; Siljander, P.R.; Laitinen, S. Lipid mediators in platelet concentrate and extracellular vesicles: Molecular mechanisms from membrane glycerophospholipids to bioactive molecules. Biochim. Biophys. Acta (BBA)—Mol. Cell Biol. Lipids 2019, 1864, 1168–1182. [Google Scholar] [CrossRef] [Scilit]
- Duchez, A.; Fauteux-Daniel, S.; Sut, C.; Ebermeyer, T.; Heestermans, M.; Arthaud, C.A.; Eyraud, M.A.; Prier, A.; Audoux, E.; Bertrand-Michel, J.; et al. Bioactive lipids as biomarkers of adverse reactions associated with apheresis platelet concentrate transfusion. Front. Immunol. 2023, 14, 1031968. [Google Scholar] [CrossRef] [Scilit]
- Roszkowska, A.; Yu, M.; Bessonneau, V.; Bragg, L.; Servos, M.; Pawliszyn, J. Tissue storage affects lipidome profiling in comparison to in vivo microsampling approach. Sci. Rep. 2018, 8, 6980. [Google Scholar] [CrossRef] [Scilit]
- Cioccari, L.; Luethi, N.; Masoodi, M. Lipid Mediators in Critically Ill Patients: A Step Towards Precision Medicine. Front. Immunol. 2020, 11, 599853. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mispelbaum, R.; Hattenhauer, T.; Brossart, P.; Heine, A. Red blood cell transfusions impact response rates to immunotherapy in patients with solid malignant tumors. Front. Immunol. 2022, 13, 976011. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aguilar-Nascimento, J.E.; Zampieri-Filho, J.P.; Bordin, J.O. Implications of perioperative allogeneic red blood cell transfusion on the immune-inflammatory response. Hematol. Transfus. Cell Ther. 2021, 43, 58–64. [Google Scholar] [CrossRef] [Scilit]
- Wu, H.L.; Tai, Y.; Lin, S.P.; Chan, M.Y.; Chen, C.; Chang, K.Y. The Impact of Blood Transfusion on Recurrence and Mortality Following Colorectal Cancer Resection: A Propensity Score Analysis of 4,030 Patients. Sci. Rep. 2018, 8, 13345. [Google Scholar] [CrossRef] [Scilit]
- Amato, A.; Pescatori, M. Perioperative blood transfusions for the recurrence of colorectal cancer. Cochrane Database Syst. Rev. 2006, 2006, CD005033. [Google Scholar] [CrossRef] [Scilit]
- Weber, R.S.; Jabbour, N.; Martin, R.C.G. Anemia and Transfusions in Patients Undergoing Surgery for Cancer. Ann. Surg. Oncol. 2008, 15, 34–45. [Google Scholar] [CrossRef] [Scilit]
- Yang, K.; Halima, A.; Chan, T.A. Antigen presentation in cancer—Mechanisms and clinical implications for immunotherapy. Nat. Rev. Clin. Oncol. 2023, 20, 604–623. [Google Scholar] [CrossRef] [Scilit]
- Adane, T.; Enawgaw, B. Human leukocyte antigen alloimmunization prevention mechanisms in blood transfusion. Asian J. Transfus. Sci. 2023, 17, 264–272. [Google Scholar] [CrossRef] [Scilit]
- Hemauer, S.J.; Kingeter, A.J.; Han, X.; Shotwell, M.S.; Pandharipande, P.P.; Weavind, L.M. Daily Lowest Hemoglobin and Risk of Organ Dysfunctions in Critically Ill Patients. Crit. Care Med. 2017, 45, e479–e484. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vamvakas, E.C.; Blajchman, M.A. Transfusion-related immunomodulation (TRIM): An update. Blood Rev. 2007, 21, 327–348. [Google Scholar] [CrossRef] [Scilit]
- Sihler, K.C.; Napolitano, L.M. Complications of massive transfusion. Chest 2010, 137, 209–220. [Google Scholar] [CrossRef] [Scilit]
- Blet, A.; McNeil, J.B.; Josse, J.; Cholley, B.; Cinotti, R.; Cotter, G.; Dauvergne, A.; Davison, B.; Duarte, K.; Duranteau, J.; et al. Association between in-ICU red blood cells transfusion and 1-year mortality in ICU survivors. Crit. Care 2022, 26, 307. [Google Scholar] [CrossRef] [Scilit]
- Blumberg, N.; Heal, J.M. Effects of transfusion on immune function. Cancer recurrence and infection. Arch Pathol. Lab. Med. 1994, 118, 371–379. [Google Scholar]
- Dellinger, E.P.; Anaya, D.A. Infectious and immunologic consequences of blood transfusion. Crit. Care 2004, 8, S18–S23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Busch, M.P.; Kleinman, S.H.; Nemo, G.J. Current and emerging infectious risks of blood transfusions. JAMA 2003, 289, 959–962. [Google Scholar] [CrossRef] [Scilit]
- Jongerius, I.; Porcelijn, L.; van Beek, A.E.; Semple, J.W.; van der Schoot, C.E.; Vlaar, A.P.J.; Kapur, R. The Role of Complement in Transfusion-Related Acute Lung Injury. Transfus. Med. Rev. 2019, 33, 236–242. [Google Scholar] [CrossRef] [Scilit]
- Roubinian, N. TACO and TRALI: Biology, risk factors, and prevention strategies. Hematol. Am. Soc. Hematol. Educ. Program 2018, 2018, 585–594. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Wonderen, S.F.; Klanderman, R.B.; Vlaar, A.P.J. Understanding transfusion-related acute lung injury (TRALI) and its complex pathophysiology. Blood Transfus. 2022, 20, 443–445. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tung, J.P.; Chiaretti, S.; Dean, M.M.; Sultana, A.J.; Reade, M.C.; Fung, Y.L. Transfusion-related acute lung injury (TRALI): Potential pathways of development, strategies for prevention and treatment, and future research directions. Blood Rev. 2022, 53, 100926. [Google Scholar] [CrossRef] [Scilit]
- Semple, J.W.; Rebetz, J.; Kapur, R. Transfusion-associated circulatory overload and transfusion-related acute lung injury. Blood 2019, 133, 1840–1853. [Google Scholar] [CrossRef] [Scilit]
- Vlaar, A.P.J.; Toy, P.; Fung, M.; Looney, M.R.; Juffermans, N.P.; Bux, J.; Bolton-Maggs, P.; Peters, A.L.; Silliman, C.C.; Kor, D.J.; et al. A consensus redefinition of transfusion-related acute lung injury. Transfusion 2019, 59, 2465–2476. [Google Scholar] [CrossRef] [Scilit]
- Yu, Y.; Lian, Z. Update on transfusion-related acute lung injury: An overview of its pathogenesis and management. Front. Immunol. 2023, 14, 1175387. [Google Scholar] [CrossRef] [Scilit]
- Lisitano, L.; Röttinger, T.; Thorne, T.; Förch, S.; Cifuentes, J.; Rau, K.; Vounatsos, P.D.; Mayr, E. A comprehensive analysis of intraoperative factors associated with acute-on-chronic kidney injury in elderly trauma patients: Blood loss as a key predictor. Aging Clin. Exp. Res. 2023, 35, 2729–2737. [Google Scholar] [CrossRef] [Scilit]
- Bulle, E.B.; Klanderman, R.B.; Pendergrast, J.; Cserti-Gazdewich, C.; Callum, J.; Vlaar, A.P.J. The recipe for TACO: A narrative review on the pathophysiology and potential mitigation strategies of transfusion-associated circulatory overload. Blood Rev. 2022, 52, 100891. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karkouti, K. Transfusion and risk of acute kidney injury in cardiac surgery. Br. J. Anaesth. 2012, 109, i29–i38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Merchant, A.M.; Neyra, J.A.; Minhajuddin, A.; Wehrmann, L.E.; Mills, R.A.; Gualano, S.K.; Kumbhani, D.J.; Huffman, L.C.; Jessen, M.E.; Fox, A.A. Packed red blood cell transfusion associates with acute kidney injury after transcatheter aortic valve replacement. BMC Anesthesiol. 2019, 19, 99. [Google Scholar] [CrossRef] [Scilit]
- Suzuki, G.; Ichibayashi, R.; Masuyama, Y.; Yamamoto, S.; Serizawa, H.; Nakamichi, Y.; Watanabe, M.; Honda, M. Association of red blood cell and platelet transfusions with persistent inflammation, immunosuppression, and catabolism syndrome in critically ill patients. Sci. Rep. 2022, 12, 629. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hayakawa, M.; Tagami, T.; Kudo, D.; Ono, K.; Aoki, M.; Endo, A.; Yumoto, T.; Matsumura, Y.; Irino, S.; Sekine, K.; et al. The Restrictive Red Blood Cell Transfusion Strategy for Critically Injured Patients (RESTRIC) trial: A cluster-randomized, crossover, non-inferiority multicenter trial of restrictive transfusion in trauma. J. Intensive Care 2023, 11, 34. [Google Scholar] [CrossRef] [Scilit]
- Kawakami, L.E.; Bonomi, P.B.; Pereira, M.A.; Carvalho, F.O.; Ribeiro, U., Jr.; Zilberstein, B.; Sampaio, L.R.; Carneiro-D’Albuquerque, L.A.; Ramos, M.F.K.P. Risk factors for blood transfusion and its prognostic implications in curative gastrectomy for gastric cancer. World J. Gastrointest. Surg. 2023, 15, 643–654. [Google Scholar] [CrossRef] [Scilit]
- Schaller, J.; Agudo, J. Metastatic Colonization: Escaping Immune Surveillance. Cancers 2020, 12, 3385. [Google Scholar] [CrossRef] [Scilit]
- Abou Daher, L.; Heppell, O.; Lopez-Plaza, I.; Guerra-Londono, C.E. Perioperative Blood Transfusions and Cancer Progression: A Narrative Review. Curr. Oncol. Rep. 2024, 26, 880–889. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Straat, M.; Böing, A.N.; Tuip-De Boer, A.; Nieuwland, R.; Juffermans, N.P. Extracellular Vesicles from Red Blood Cell Products Induce a Strong Pro-Inflammatory Host Response, Dependent on Both Numbers and Storage Duration. Transfus. Med. Hemother. 2016, 43, 302–305. [Google Scholar] [CrossRef] [Scilit]
- Rebulla, P.; Prati, D. Pathogen Reduction for Platelets-A Review of Recent Implementation Strategies. Pathogens 2022, 11, 142. [Google Scholar] [CrossRef] [Scilit]
- Loftus, T.J.; Thomas, R.M.; Murphy, T.W.; Nguyen, L.L.; Moore, F.A.; Brakenridge, S.C.; Efron, P.A.; Mohr, A.M. The effects of red cell transfusion donor age on nosocomial infection among trauma patients. Am. J. Surg. 2017, 214, 672–676. [Google Scholar] [CrossRef] [Scilit]
- Paglino, J.C.; Pomper, G.J.; Fisch, G.S.; Champion, M.H.; Snyder, E.L. Reduction of febrile but not allergic reactions to RBCs and platelets after conversion to universal prestorage leukoreduction. Transfusion 2004, 44, 16–24. [Google Scholar] [CrossRef] [Scilit]
- Antonelou, M.H.; Tzounakas, V.L.; Velentzas, A.D.; Stamoulis, K.E.; Kriebardis, A.G.; Papassideri, I.S. Effects of pre-storage leukoreduction on stored red blood cells signaling: A time-course evaluation from shape to proteome. J. Proteom. 2012, 76, 220–238. [Google Scholar] [CrossRef] [Scilit]
- Dzik, S. Prestorage leukocyte reduction of cellular blood components. Transfus. Sci. 1994, 15, 131–139. [Google Scholar] [CrossRef] [Scilit]
- Dejigov Monteiro da Silva, N.; Nukui, Y.; Takahashi, J.; de Almeida Lopes Monteiro da Cruz, D.; de Souza Nogueira, L. Effect of post-storage filters vs. pre-storage filters for leukoreduction of blood components on clinical outcomes: A systematic review and meta-analysis. Syst. Rev. 2024, 13, 196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bianchi, M.; Vaglio, S.; Pupella, S.; Marano, G.; Facco, G.; Liumbruno, G.M.; Grazzini, G. Leucoreduction of blood components: An effective way to increase blood safety? Blood Transfus. 2016, 14, 214–227. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mabilangan, C.; Burton, C.; Nahirniak, S.; O’Brien, S.; Preiksaitis, J. Transfusion-transmitted and community-acquired cytomegalovirus infection in seronegative solid organ transplant recipients receiving seronegative donor organs. Am. J. Transplant. 2020, 20, 3509–3519. [Google Scholar] [CrossRef] [Scilit]
- Jebakumar, D.; Bryant, P.; Linz, W. Risk of cytomegalovirus transmission by blood products after solid organ transplantation. Bayl. Univ. Med. Cent. Proc. 2019, 32, 222–226. [Google Scholar] [CrossRef] [Scilit]
- Voruz, S.; Gowland, P.; Eyer, C.; Widmer, N.; Abonnenc, M.; Prudent, M.; Masouridi-Levrat, S.; Duchosal, M.A.; Niederhauser, C. Transfusion-transmitted cytomegalovirus: Behaviour of cell-free virus during blood component processing. A study on the safety of labile blood components in Switzerland. Blood Transfus. 2020, 18, 446–453. [Google Scholar] [CrossRef] [Scilit]
- Cesaro, S.; Ljungman, P.; Tridello, G.; Mikulska, M.; Wendel, L.; Styczynski, J.; Averbuch, D.; de la Camara, R. New trends in the management of cytomegalovirus infection after allogeneic hematopoietic cell transplantation: A survey of the Infectious Diseases Working Pary of EBMT. Bone Marrow Transplant. 2023, 58, 203–208. [Google Scholar] [CrossRef] [Scilit]
- Dobson, G.P.; Morris, J.L.; Letson, H.L. Immune dysfunction following severe trauma: A systems failure from the central nervous system to mitochondria. Front. Med. 2022, 9, 968453. [Google Scholar] [CrossRef] [Scilit]
- Lim, A.R.; Kim, J.H.; Hyun, M.H.; Chang, W.J.; Lee, S.; Kim, Y.H.; Park, K.H.; Park, J.H. Blood transfusion has an adverse impact on the prognosis of patients receiving chemotherapy for advanced colorectal cancer: Experience from a single institution with a patient blood management program. Support. Care Cancer 2022, 30, 5289–5297. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basavarajegowda, A.; Plakkal, N. Transfusion reactions in neonates and pediatrics: How and why are they different? Asian J. Transfus. Sci. 2023, 17, 97–102. [Google Scholar] [CrossRef] [Scilit]
- Shander, A.; Hardy, J.F.; Ozawa, S.; Farmer, S.L.; Hofmann, A.; Frank, S.M.; Kor, D.J.; Faraoni, D.; Freedman, J.; Collaborators. A Global Definition of Patient Blood Management. Anesth. Analg. 2022, 135, 476–488. [Google Scholar] [CrossRef] [Scilit]
- Hofmann, A.; Spahn, D.R.; Holtorf, A.P.; PBM Implementation Group. Making patient blood management the new norm(al) as experienced by implementors in diverse countries. BMC Health Serv. Res. 2021, 21, 634. [Google Scholar] [CrossRef] [Scilit]
- Pérez-Calatayud, A.A.; Hofmann, A.; Pérez-Ferrer, A.; Escorza-Molina, C.; Torres-Pérez, B.; Zaccarias-Ezzat, J.R.; Sanchez-Cedillo, A.; Manuel Paez-Zayas, V.; Carrillo-Esper, R.; Görlinger, K. Patient Blood Management in Liver Transplant-A Concise Review. Biomedicines 2023, 11, 1093. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Permpikul, C.; Tanksinmankhong, J.; Tongyoo, S.; Naorungroj, T.; Viarasilpa, T.; Karaketklang, K. Optimal hemoglobin threshold for blood transfusions in sepsis and septic shock: A retrospective analysis. Intern. Emerg. Med. 2025, 20, 829–839. [Google Scholar] [CrossRef] [Scilit]
- Goodnough, L.T.; Shah, N. Is there a “magic” hemoglobin number? Clinical decision support promoting restrictive blood transfusion practices. Am. J. Hematol. 2015, 90, 927–933. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Applefeld, W.N.; Ford, V.J.; Cortes-Puch, I.; Wang, J.; Sun, J.; Shields, T.C.; Danner, R.L.; Eichacker, P.Q.; Solomon, M.A.; Klein, H.G.; et al. Risks of Restrictive Versus Liberal Red Blood Cell Transfusion Strategies in Patients with Cardiovascular Disease: An Updated Meta-Analysis. Circ. Cardiovasc. Qual. Outcomes 2024, 17, e010957. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garland-Kledzik, M.; Gaffley, M.; Crouse, D.; Conrad, C.; Miller, P.; Martin, R.S. Effects of a More Restrictive Transfusion Trigger in Trauma Patients. Am. Surg. 2019, 85, 409–413. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blanca, D.; Parrella, G.; Consonni, D.; Villa, S.; Ceriani, G.; Cespiati, A.; Figini, G.; Ghigliazza, G.; Maira, D.; Oberti, G.; et al. Anemia management and transfusion strategy in internal medicine units: Less is more. Eur. J. Intern. Med. 2023, 115, 48–54. [Google Scholar] [CrossRef] [Scilit]
- Carson, J.L.; Brooks, M.M.; Hébert, P.C.; Goodman, S.G.; Bertolet, M.; Glynn, S.A.; Chaitman, B.R.; Simon, T.; Lopes, R.D.; Goldsweig, A.M.; et al. MINT Investigators. Restrictive or Liberal Transfusion Strategy in Myocardial Infarction and Anemia. N. Engl. J. Med. 2023, 389, 2446–2456. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mirski, M.A.; Frank, S.M.; Kor, D.J.; Vincent, J.L.; Holmes, D.R., Jr. Restrictive and liberal red cell transfusion strategies in adult patients: Reconciling clinical data with best practice. Crit. Care 2015, 19, 202. [Google Scholar] [CrossRef] [Scilit]
- Vlaar, A.P.; Oczkowski, S.; de Bruin, S.; Wijnberge, M.; Antonelli, M.; Aubron, C.; Aries, P.; Duranteau, J.; Juffermans, N.P.; Meier, J.; et al. Transfusion strategies in non-bleeding critically ill adults: A clinical practice guideline from the European Society of Intensive Care Medicine. Intensive Care Med. 2020, 46, 673–696. [Google Scholar] [CrossRef] [Scilit]
- Leahy, M.F.; Hofmann, A.; Towler, S.; Trentino, K.M.; Burrows, S.A.; Swain, S.G.; Hamdorf, J.; Gallagher, T.; Koay, A.; Geelhoed, G.C.; et al. Improved outcomes and reduced costs associated with a health-system-wide patient blood management program: A retrospective observational study in four major adult tertiary-care hospitals. Transfusion 2017, 57, 1347–1358. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ozawa, S.; Isbister, J.P.; Farmer, S.L.; Hofmann, A.; Ozawa-Morriello, J.; Gross, I.; Shander, A. Blood Health: The Ultimate Aim of Patient Blood Management. Anesth. Analg. 2025, 141, 950–955. [Google Scholar] [CrossRef] [Scilit]
- Hofmann, A.; Aapro, M.; Fedorova, T.A.; Zhiburt, Y.B.; Snegovoy, A.V.; Kaganov, O.I.; Ognerubov, N.A.; Lyadov, V.K.; Moiseenko, V.M.; Trofimova, O.P.; et al. Patient blood management in oncology in the Russian Federation: Resolution to improve oncology care. J. Cancer Policy 2022, 31, 100315. [Google Scholar] [CrossRef] [Scilit]
- Ansari, T.; Wani, S.; Hofmann, A.; Shetty, N.; Sangani, K.; Stamp, C.J.; Murray, K.; Trentino, K.M. Outcomes Associated with a Patient Blood Management Program in Major Obstetric Hemorrhage: A Retrospective Cohort Study. Anesth. Analg. 2026, 142, 114–123. [Google Scholar] [CrossRef] [Scilit]
- Trentino, K.M.; Farmer, S.L.; Isbister, J.P.; Sanfilippo, F.M.; Leahy, M.F.; Hofmann, A.; Shander, A.; Murray, K. Restrictive Versus Liberal Transfusion Trials: Are They Asking the Right Question? Anesth. Analg. 2020, 131, 1950–1955. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shander, A.; Goobie, S.M.; Warner, M.A.; Aapro, M.; Bisbe, E.; Perez-Calatayud, A.A.; Callum, J.; Cushing, M.M.; Dyer, W.B.; Erhard, J.; et al. International Foundation of Patient Blood Management (IFPBM) and Society for the Advancement of Blood Management (SABM) Work Group. Essential Role of Patient Blood Management in a Pandemic: A Call for Action. Anesth. Analg. 2020, 131, 74–85. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Trentino, K.M.; Farmer, S.L.; Leahy, M.F.; Sanfilippo, F.M.; Isbister, J.P.; Mayberry, R.; Hofmann, A.; Shander, A.; French, C.; Murray, K. Systematic reviews and meta-analyses comparing mortality in restrictive and liberal haemoglobin thresholds for red cell transfusion: An overview of systematic reviews. BMC Med. 2020, 18, 154. [Google Scholar] [CrossRef] [Scilit]
- Trentino, K.M.; Farmer, S.L.; Sanfilippo, F.M.; Leahy, M.F.; Isbister, J.; Mayberry, R.; Hofmann, A.; Murray, K. Systematic reviews and meta-analyses comparing mortality in restrictive and liberal haemoglobin thresholds for red cell transfusion: Protocol for an overview of systematic reviews. BMJ Open 2019, 9, e029828. [Google Scholar] [CrossRef] [Scilit]
- Khan, S.H.; Devnani, R.; LaPradd, M.; Landrigan, M.; Gray, A.; Kelley, A.; Eckert, G.J.; Li, X.; Khan, B.A. Age of transfused red blood cells and health outcomes in two surgical cohorts. Heart Lung 2019, 48, 131–137. [Google Scholar] [CrossRef] [Scilit]
- Wise, T.J.; Ott, M.E.; Joseph, M.S.; Welsby, I.J.; Darrow, C.C.; McMahon, T.J. Modulation of the allosteric and vasoregulatory arms of erythrocytic oxygen transport. Front. Physiol. 2024, 15, 1394650. [Google Scholar] [CrossRef] [Scilit]
- Raeven, P.; Karlhofer, K.; Sztulman, L.S.; Brugger, J.; Hoetzenecker, K.; Domenig, C.; Leitner, G.; Posch, M.; Baron, D.M.; Spittler, A. Red blood cell transfusion-related dynamics of extracellular vesicles in intensive care patients: A prospective subanalysis. Sci. Rep. 2024, 14, 911. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jacka, M.; Nahirniak, S.; ACP Journal Club. In critically ill adults, transfusion of fresh vs standard-issue red blood cells did not differ for 90-day mortality. Ann. Intern. Med. 2015, 163, JC5. [Google Scholar] [CrossRef] [Scilit]
- Kong, Y.; Tian, X.; He, R.; Li, C.; Xu, H.; Tian, L.; Liu, Z. The accumulation of exosome-associated microRNA-1246 and microRNA-150-3p in human red blood cell suspensions. J. Transl. Med. 2021, 19, 225. [Google Scholar] [CrossRef] [Scilit]
- Sivakaanthan, A.; Swain, F.; Pahn, G.; Goodison, K.; Gutta, N.; Holdsworth, R.; Baidya, S.; Tung, J.P. Transfusion-related acute lung injury (TRALI): A retrospective review of reported cases in Queensland, Australia over 20 years. Blood Transfus. 2022, 20, 454–464. [Google Scholar] [CrossRef] [Scilit]
- Joshi, U.; George, L.B.; Highland, H. Red blood cell extracellular vesicles: New frontiers in hematological biomarker discovery. Front. Med. 2025, 12, 1644077. [Google Scholar] [CrossRef] [Scilit]
- Leventhal, J.; Abecassis, M.; Miller, J.; Gallon, L.; Ravindra, K.; Tollerud, D.J.; King, B.; Elliott, M.J.; Herzig, G.; Herzig, R.; et al. Chimerism and tolerance without GVHD or engraftment syndrome in HLA-mismatched combined kidney and hematopoietic stem cell transplantation. Sci. Transl. Med. 2012, 4, 124ra28. [Google Scholar] [CrossRef] [Scilit]
- Hotta, K.; Aoyama, A.; Oura, T.; Yamada, Y.; Tonsho, M.; Huh, K.H.; Kawai, K.; Schoenfeld, D.; Allan, J.S.; Madsen, J.C.; et al. Induced regulatory T cells in allograft tolerance via transient mixed chimerism. JCI Insight 2016, 1, e86419. [Google Scholar] [CrossRef] [Scilit]
- Palviainen, M.; Puutio, J.; Østergaard, R.H.; Eble, J.A.; Maaninka, K.; Butt, U.; Ndika, J.; Kari, O.K.; Kamali-Moghaddam, M.; Kjaer-Sorensen, K.; et al. Beyond basic characterization and omics: Immunomodulatory roles of platelet-derived extracellular vesicles unveiled by functional testing. J. Extracell. Vesicles 2024, 13, e12513, Correction in J. Extracell. Vesicles 2024, 13, e70015. [Google Scholar] [CrossRef] [Scilit]
- Patlán, M.; Sánchez-Muñoz, F.; Amezcua-Guerra, L.M.; Granados, A.; Páez, A.; Massó, F.; Soster, A.; Bojalil, R.; Pavón, L.; Jiménez-Zamudio, L.A.; et al. Effect of fresh frozen plasma on the in vitro activation of U937 monocytes: A potential role for the age of blood donors and their underlying cytokine profile. Biol. Res. 2017, 50, 42. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taghavi, S.; Jackson-Weaver, O.; Abdullah, S.; Goldberg, A.; Lawicki, S.; Killackey, M.; Duchesne, J.; Pociask, D.; Steele, C.; Kolls, J. A Comparison of Growth Factors and Cytokines in Fresh Frozen Plasma and Never Frozen Plasma. J. Surg. Res. 2021, 264, 51–57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tamagne, M.; Khelfa, M.; Many, S.; Neyrinck-Leglantier, D.; Delorme, A.S.; Pinheiro, M.K.; Andrieu, M.; Cleophax, S.; Pirenne, F.; Vingert, B. Interactions with and activation of immune cells by CD41a+ extracellular vesicles. Front. Immunol. 2025, 16, 1509078. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van der Velden, S.; van Osch, T.L.J.; Seghier, A.; Bentlage, A.E.H.; Mok, J.Y.; Geerdes, D.M.; van Esch, W.J.E.; Pouw, R.B.; Brouwer, M.C. Complement activation drives antibody-mediated transfusion-related acute lung injury via macrophage trafficking and formation of NETs. Blood 2024, 143, 79–91. [Google Scholar] [CrossRef] [Scilit]
- Görlinger, K.; Pérez-Ferrer, A.; Dirkmann, D.; Saner, F.; Maegele, M.; Calatayud, Á.A.P.; Kim, T.Y. The role of evidence-based algorithms for rotational thromboelastometry-guided bleeding management. Korean J. Anesthesiol. 2019, 72, 297–322. [Google Scholar] [CrossRef] [Scilit]
- Aslam, R.; Speck, E.R.; Kim, M.; Freedman, J.; Semple, J.W. Transfusion-related immunomodulation by platelets is dependent on their expression of MHC Class I molecules and is independent of white cells. Transfusion 2008, 48, 1778–1786. [Google Scholar] [CrossRef] [Scilit]
- Guo, K.; Ma, S. The Immune System in Transfusion-Related Acute Lung Injury Prevention and Therapy: Update and Perspective. Front. Mol. Biosci. 2021, 8, 639976, Erratum in: Front. Mol. Biosci. 2021, 8, 720653. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, S.J.; Wang, H.; Ahn, S.H.; Son, M.K.; Hyun, G.H.; Yoon, S.J.; Lee, J.; Park, J.H.; Lim, J.; Hong, S.S.; et al. Metabolomics Approach Based on Multivariate Techniques for Blood Transfusion Reactions. Sci. Rep. 2019, 9, 1740. [Google Scholar] [CrossRef] [Scilit]
- Block, H.; Rossaint, J.; Zarbock, A. The Fatal Circle of NETs and NET-Associated DAMPs Contributing to Organ Dysfunction. Cells 2022, 11, 1919. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, F.; Bai, Y.; Xiang, X.; Pang, X. The role of fibromodulin in inflammatory responses and diseases associated with inflammation. Front. Immunol. 2023, 14, 1191787. [Google Scholar] [CrossRef] [Scilit]
- Stanford, S.; Roy, A.; Cecil, T.; Hegener, O.; Schulz, P.; Turaj, A.; Lim, S.; Arbuthnot, E. Differences in coagulation-relevant parameters: Comparing cryoprecipitate and a human fibrinogen concentrate. PLoS ONE 2023, 18, e0290571. [Google Scholar] [CrossRef] [Scilit]
- LaCroix, I.S.; Cohen, M.J.; Moore, E.E.; Dzieciątkowska, M.; Nemkov, T.; Schaid, T.R.; Debot, M.; Jones, K.; Silliman, C.C.; Hansen, K.C.; et al. Omics Markers of Red Blood Cell Transfusion in Trauma. Int. J. Mol. Sci. 2022, 23, 13815. [Google Scholar] [CrossRef] [Scilit]
- Neal, M.D.; Raval, J.S.; Triulzi, D.J.; Simmons, R.L. Innate immune activation after transfusion of stored red blood cells. Transfus. Med. Rev. 2013, 27, 113–118. [Google Scholar] [CrossRef] [Scilit]
- Moriyama, K.; Nishida, O. Targeting Cytokines, Pathogen-Associated Molecular Patterns, and Damage-Associated Molecular Patterns in Sepsis via Blood Purification. Int. J. Mol. Sci. 2021, 22, 8882. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xiang, M.; Fan, J.; Fan, J. Association of Toll-Like Receptor Signaling and Reactive Oxygen Species: A Potential Therapeutic Target for Posttrauma Acute Lung Injury. Mediat. Inflamm. 2010, 2010, 916425. [Google Scholar] [CrossRef] [Scilit]
- Yokoyama, A.P.H.; Kutner, J.M.; de Moraes Mazetto Fonseca, B.; Mesquita, G.L.T.V.; Sakashita, A.M.; dos Santos, A.P.R.; Nakazawa, C.Y.; de Almeida, M.D.; Orsi, F.L.A. Neutrophil extracellular traps (NETs), transfusion requirements and clinical outcomes in orthotopic liver transplantation. J. Thromb. Thrombolysis 2023, 56, 253. [Google Scholar] [CrossRef] [Scilit]
- Vorobjeva, N.V.; Chernyak, B.V. NETosis: Molecular Mechanisms, Role in Physiology and Pathology. Biochemistry 2020, 85, 1178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, D.; Tian, K.; Xu, X.; Xia, W.; Ye, X.; Wu, Y.-B.; Xu, Y.R.; Liu, J.; Ren, H.; Deng, J.; et al. Mechanism and intervention of murine transfusion-related acute lung injury caused by anti-CD36 antibodies. JCI Insight 2023, 8, e165142. [Google Scholar] [CrossRef] [Scilit]
- Carney, P.R.; Zarzaur, B.L.; Holcomb, J.B.; Fox, E.E.; Wade, C.E.; Savage, S.A. The impact of transfusion kinetics on the inflammatory response following major injury. J. Trauma Acute Care Surg. 2024, 97, 904. [Google Scholar] [CrossRef] [Scilit]
- Zimring, J.C.; Hudson, K.E.; Hendrickson, J.E. Innate and adaptive immune responses to transfused alloantigens. Pathology 2015, 47, S34. [Google Scholar] [CrossRef] [Scilit]
- Tian, J.-W.; Zhang, H.; Siyuan, L.; Guo, Y.-L.; Chen, G.; Yu, Z. Tumor Cell-derived Extracellular Vesicles in Modulating Phenotypes and Immune Functions of Macrophages: Mechanisms and Therapeutic Applications. J. Cancer 2023, 14, 1321. [Google Scholar] [CrossRef] [Scilit]
- Ma, F.; Vayalil, J.; Lee, G.; Wang, Y.; Peng, G. Emerging role of tumor-derived extracellular vesicles in T cell suppression and dysfunction in the tumor microenvironment. J. Immunother. Cancer 2021, 9, e003217. [Google Scholar] [CrossRef] [Scilit]
- Ma, X.; Liu, Y.; Han, Q.; Han, Y.; Wang, J.; Zhang, H. Transfusion-related immunomodulation in patients with cancer: Focus on the impact of extracellular vesicles from stored red blood cells (Review). Int. J. Oncol. 2021, 59, 108. [Google Scholar] [CrossRef] [Scilit]
- Delorme, A.S.; Laguide, A.; Tamagne, M.; Pinheiro, M.K.; Cagnet, L.; Neyrinck-Leglantier, D.; Khelfa, M.; Cleophax, S.; Pirenne, F.; Vingert, B. Immune interactions and regulation with CD39+ extracellular vesicles from platelet concentrates. Front. Immunol. 2024, 15, 1397967. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Almizraq, R.J.; Seghatchian, J.; Acker, J.P. Extracellular vesicles in transfusion-related immunomodulation and the role of blood component manufacturing. Transfus. Apher. Sci. 2016, 55, 281. [Google Scholar] [CrossRef] [Scilit]
- Alberro, A.; Iparraguirre, L.; Fernandes, A.; Otaegui, D. Extracellular Vesicles in Blood: Sources, Effects, and Applications. Int. J. Mol. Sci. 2021, 22, 8163. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thangaraju, K.; Neerukonda, S.N.; Katneni, U.; Buehler, P.W. Extracellular Vesicles from Red Blood Cells and Their Evolving Roles in Health, Coagulopathy and Therapy. Int. J. Mol. Sci. 2020, 22, 153. [Google Scholar] [CrossRef] [Scilit]
- Sonego, G.; Abonnenc, M.; Tissot, J.; Prudent, M.; Lion, N. Redox Proteomics and Platelet Activation: Understanding the Redox Proteome to Improve Platelet Quality for Transfusion. Int. J. Mol. Sci. 2017, 18, 387. [Google Scholar] [CrossRef] [Scilit]
- Andersson, L.; Sjöström, D.J.; Quach, H.Q.; Hägerström, K.; Hurler, L.; Kajdácsi, E.; Cervenak, L.; Prohászka, Z.; Toonen, E.J.M.; Mohlin, C.; et al. Storage of Transfusion Platelet Concentrates Is Associated with Complement Activation and Reduced Ability of Platelets to Respond to Protease-Activated Receptor-1 and Thromboxane A2 Receptor. Int. J. Mol. Sci. 2024, 25, 1091. [Google Scholar] [CrossRef] [Scilit]
- Liu, Y.; Wang, R.; Song, C.; Ding, S.; Zuo, Y.; Yi, K.; Li, N.; Wang, B.; Geng, Q. Crosstalk between neutrophil extracellular traps and immune regulation: Insights into pathobiology and therapeutic implications of transfusion-related acute lung injury. Front. Immunol. 2023, 14, 1324021. [Google Scholar] [CrossRef] [Scilit]
- Zifkos, K.; Dubois, C.; Schäfer, K. Extracellular Vesicles and Thrombosis: Update on the Clinical and Experimental Evidence. Int. J. Mol. Sci. 2021, 22, 9317. [Google Scholar] [CrossRef] [Scilit]
- Zhang, H.; Zhou, Y.; Qu, M.; Yu, Y.; Chen, Z.; Zhu, S.; Guo, K.; Chen, W.; Miao, C. Tissue Factor-Enriched Neutrophil Extracellular Traps Promote Immunothrombosis and Disease Progression in Sepsis-Induced Lung Injury. Front. Cell. Infect. Microbiol. 2021, 11, 677902. [Google Scholar] [CrossRef] [Scilit]
- Blanch-Ruiz, M.A.; Ortega-Luna, R.; Martínez-Cuesta, M.Á.; Álvarez, Á. The Neutrophil Secretome as a Crucial Link between Inflammation and Thrombosis. Int. J. Mol. Sci. 2021, 22, 4170. [Google Scholar] [CrossRef] [Scilit]
- Pfister, H. Neutrophil Extracellular Traps and Neutrophil-Derived Extracellular Vesicles: Common Players in Neutrophil Effector Functions. Diagnostics 2022, 12, 1715. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schiavello, M.; Vizio, B.; Bosco, O.; Pivetta, E.; Mariano, F.; Montrucchio, G.; Lupia, E. Extracellular Vesicles: New Players in the Mechanisms of Sepsis- and COVID-19-Related Thromboinflammation. Int. J. Mol. Sci. 2023, 24, 1920. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Groten, S.A.; Smit, E.R.; Janssen, E.F.J.; van den Eshof, B.L.; van Alphen, F.P.J.; van der Zwaan, C.; Meijer, A.B.; Hoogendijk, A.J.; van den Biggelaar, M. Multiomics delineation of cytokine-induced endothelial inflammatory states. Commun. Biol. 2023, 6, 525. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Theofilis, P.; Sagris, Μ.; Oikonomou, E.; Antonopoulos, A.S.; Siasos, G.; Tsioufis, C.; Tousoulis, D. Inflammatory Mechanisms Contributing to Endothelial Dysfunction. Biomedicines 2021, 9, 781. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muszynski, J.A.; Spinella, P.C.; Cholette, J.M.; Acker, J.P.; Hall, M.W.; Juffermans, N.P.; Kelly, D.P.; Blumberg, N.; Nicol, K.; Liedel, J. Transfusion-related immunomodulation: Review of the literature and implications for pediatric critical illness. Transfusion 2016, 57, 195. [Google Scholar] [CrossRef] [Scilit]
- Smith, D.M., Jr. Immunosuppressive Effects of Blood Transfusion. Clin. Lab. Med. 1992, 12, 723–741. [Google Scholar] [CrossRef] [Scilit]
- Diebold, M.; Farkash, E.A.; Barnes, J.; Regele, H.; Kozakowski, N.; Schatzl, M.; Mayer, K.A.; Haindl, S.; Vietzen, H.; Hidalgo, L.G.; et al. Natural Killer Cell Presence in Antibody-Mediated Rejection. Transpl. Int. 2024, 37, 13209. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cacalano, N.A. Regulation of Natural Killer Cell Function by STAT3. Front. Immunol. 2016, 7, 128. [Google Scholar] [CrossRef] [Scilit]
- Schioppa, T.; Gaudenzi, C.; Zucchi, G.; Piserà, A.; Vahidi, Y.; Tiberio, L.; Mayer, K.A.; Haindl, S.; Vietzen, H.; Hidalgo, L.G.; et al. Extracellular vesicles at the crossroad between cancer progression and immunotherapy: Focus on dendritic cells. J. Transl. Med. 2024, 22, 691. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hong, C.; Jin, R.; Dai, X.; Gao, X. Functional Contributions of Antigen Presenting Cells in Chronic Graft-Versus-Host Disease. Front. Immunol. 2021, 12, 614183. [Google Scholar] [CrossRef] [Scilit]
- Verdon, D.J.; Mulazzani, M.; Jenkins, M.R. Cellular and Molecular Mechanisms of CD8+ T Cell Differentiation, Dysfunction and Exhaustion. Int. J. Mol. Sci. 2020, 21, 7357. [Google Scholar] [CrossRef] [Scilit]
- Papareddy, P.; Tapken, I.; Kroh, K.; Bhongir, R.K.V.; Rahman, M.; Baumgarten, M.; Cim, E.I.; Györffy, L.; Smeds, E.; Neumann, A.; et al. The role of extracellular vesicle fusion with target cells in triggering systemic inflammation. Nat. Commun. 2024, 15, 1150. [Google Scholar] [CrossRef] [Scilit]
- Hwang, H.S.; Kim, H.; Han, G.; Lee, J.W.; Kim, K.; Kwon, I.C.; Yang, Y.; Kim, S.H. Extracellular Vesicles as Potential Therapeutics for Inflammatory Diseases. Int. J. Mol. Sci. 2021, 22, 5487. [Google Scholar] [CrossRef] [Scilit]
- Di Mambro, T.; Pellielo, G.; Agyapong, E.D.; Carinci, M.; Chianese, D.; Giorgi, C.; Morciano, G.; Patergnani, S.; Pinton, P.; Rimessi, A. The Tricky Connection between Extracellular Vesicles and Mitochondria in Inflammatory-Related Diseases. Int. J. Mol. Sci. 2023, 24, 8181. [Google Scholar] [CrossRef] [Scilit]
- Ebeyer-Masotta, M.; Eichhorn, T.; Fischer, M.B.; Weber, V. Impact of production methods and storage conditions on extracellular vesicles in packed red blood cells and platelet concentrates. Transfus. Apher. Sci. 2024, 63, 103891. [Google Scholar] [CrossRef] [Scilit]
- Fernández-Sojo, J.; Horton, R.; Cid, J.; Azqueta, C.; Garcia-Buendia, A.; Valdivia, E.; Martorell, L.; Rubio-Lopez, N.; Codinach, M.; Aran, G.; et al. Leukocytapheresis variables and transit time for allogeneic cryopreserved hpc: Better safe than sorry. Bone Marrow Transplant. 2022, 57, 1531–1538. [Google Scholar] [CrossRef] [Scilit]
- Kaur, D.; Sharma, R.R.; Marwaha, N. Defining an appropriate leucoreduction strategy by serial assessment of cytokine levels in platelet concentrates prepared by different methods. Asian J. Transfus. Sci. 2015, 9, 31–35. [Google Scholar] [CrossRef] [Scilit]
- Pertinhez, T.A.; Casali, E.; Baroni, F.; Berni, P.; Baricchi, R.; Spisni, A. A Comparative Study of the Effect of Leukoreduction and Pre-storage Leukodepletion on Red Blood Cells during Storage. Front. Mol. Biosci. 2016, 3, 13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coz Yataco, A.O.; Soghier, I.; Hébert, P.C.; Belley-Cote, E.; Disselkamp, M.; Flynn, D.; Halvorson, K.; Iaccarino, J.M.; Lim, W.; Lindenmeyer, C.C.; et al. Red Blood Cell Transfusion in Critically Ill Adults: An American College of Chest Physicians Clinical Practice Guideline. Chest 2025, 167, 477–489. [Google Scholar] [CrossRef] [Scilit]
- Cardoso, M.; Ragan, I.; Hartson, L.; Goodrich, R.P. Emerging Pathogen Threats in Transfusion Medicine: Improving Safety and Confidence with Pathogen Reduction Technologies. Pathogens 2023, 12, 911. [Google Scholar] [CrossRef] [Scilit]
- Lam, L.; Klingensmith, N.J.; Sayegh, L.; Oatman, E.; Jose, J.; Cosgriff, C.V.; Eckart, K.A.; McGinnis, J.; Ranjan, P.; Lanza, M.; et al. Red blood cells capture and deliver bacterial DNA to drive host responses during polymicrobial sepsis. J. Clin. Investig. 2024, 135, e182127. [Google Scholar] [CrossRef] [Scilit]
- Tran, L.N.T.; González-Fernández, C.; Gomez-Pastora, J. Impact of Different Red Blood Cell Storage Solutions and Conditions on Cell Function and Viability: A Systematic Review. Biomolecules 2024, 14, 813. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alayash, A.I. Hemoglobin Oxidation Reactions in Stored Blood. Antioxidants 2022, 11, 747. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anastasiadi, A.T.; Stamoulis, K.; Kriebardis, A.G.; Tzounakas, V.L. Molecular modifications to mitigate oxidative stress and improve red blood cell storability. Front. Physiol. 2024, 15, 1499308. [Google Scholar] [CrossRef] [Scilit]
- Raasveld, J.; Bruin Sde Reuland, M.C.; Oord Cvan den Schenk, J.; Aubron, C.; Bakker, J.; Cecconi, M.; Feldheiser, A.; Meier, J.; Müller, M.C.A.; InPUT Study Group; et al. Red Blood Cell Transfusion in the Intensive Care Unit. JAMA 2023, 330, 1852–1861. [Google Scholar] [CrossRef] [Scilit]
- Rahav Koren, R.; Suriu, C.; Yakir, O.; Akria, L.; Barhoum, M.; Braester, A. Physicians’ lack of knowledge a possible reason for red blood cell transfusion overuse? Isr. J. Health Policy Res. 2017, 6, 49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schaap, C.M.; Klanderman, R.B.; Peters, A.L.; Vlaar, A.P.J.; Müller, M.C.A. Ultra-Restrictive Transfusion Thresholds in Critically Ill. Adults: Are We Ready for the Next Step? Transfus. Med. Rev. 2025, 39, 150893. [Google Scholar] [CrossRef] [Scilit]
- Duchez, A.C.; Arthaud, C.A.; Eyraud, M.A.; Prier, A.; Heestermans, M.; Hamzeh-Cognasse, H.; Cognasse, F. Identification of new bioactive molecules in platelet preparation, storage, and transfusion reactions for improved transfusion management. Sci. Rep. 2024, 14, 29381. [Google Scholar] [CrossRef] [Scilit]
- Markham, C.; Small, S.; Hovmand, P.; Doctor, A. Transfusion Decision Making in Pediatric Critical Illness. Pediatr. Clin. N. Am. 2017, 64, 991–1015, Erratum in Pediatr. Clin. N. Am. 2018, 65, xv. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hart, S.; Cserti-Gazdewich, C.M.; McCluskey, S.A. Red cell transfusion and the immune system. Anaesthesia 2015, 70, 38-e16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vlaar, A.P.J.; Dionne, J.C.; de Bruin, S.; Wijnberge, M.; Raasveld, J.; van Baarle, F.E.H.P.; Antonelli, M.; Aubron, C.; Duranteau, J.; Juffermans, N.P.; et al. Transfusion strategies in bleeding critically ill adults: A clinical practice guideline from the European Society of Intensive Care Medicine. Intensive Care Med. 2021, 47, 1368–1392. [Google Scholar] [CrossRef] [Scilit]
- Ștefan, M.; Tomescu, D.; Predoi, C.; Goicea, R.; Perescu, M.; Popescu, M.; Dorobanțu, D.; Droc, G.; Andrei, Ș.; Știru, O.; et al. Less (Transfusion) Is More-Enhancing Recovery through Implementation of Patient Blood Management in Cardiac Surgery: A Retrospective, Single-Centre Study of 1174 Patients. J. Cardiovasc. Dev. Dis. 2023, 10, 266. [Google Scholar] [CrossRef] [Scilit]
- Céspedes, I.C.; Figueiredo, M.S.; Hossne, N.A.; Suriano, Í.C.; de Cássia Rodrigues, R.; Barros, M.M.O.; de Paiva Neto, M.A.; Atallah, F.C.; Benini, B.B.; Gonzalez, A.M.; et al. Patient Blood Management Program Implementation: Comprehensive Recommendations and Practical Strategies. Braz. J. Cardiovasc. Surg. 2024, 39, e20240205. [Google Scholar] [CrossRef] [Scilit]
- Shah, A.; Oczkowski, S.; Aubron, C.; Vlaar, A.P.; Dionne, J.C.; ESICM Transfusion Task Force. Transfusion in critical care: Past, present and future. Transfus. Med. 2020, 30, 418–432. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schmidbauer, S.L.; Seyfried, T.F. Cell Salvage at the ICU. J. Clin. Med. 2022, 11, 3848. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hof, L.; Choorapoikayil, S.; Meybohm, P.; Zacharowski, K. Patient Blood Management in intensive care patients. Curr. Opin. Crit. Care 2021, 27, 709–716. [Google Scholar] [CrossRef] [Scilit] [PubMed]


| Molecular Mechanism | Key Pathways | Clinical Consequences |
|---|---|---|
| Allogeneic leukocytes & microchimerism | Persistence of donor leukocytes, NK cell suppression, Treg expansion | Increased risk of infections, impaired immune surveillance |
| Cytokine & chemokine release | IL-6, IL-10, TNF-α, TGF-β accumulation during storage | Immunosuppression, systemic inflammation, “two-hit” amplification in sepsis/trauma |
| Extracellular vesicles & microparticles | Release of oxidized lipids, proteins, nucleic acids from stored cells | Endothelial injury, oxidative stress, altered coagulation, proinflammatory signaling |
| Bioactive lipids & storage lesion | Lysophosphatidylcholines, lipid peroxidation products | Neutrophil priming, TRALI risk, exaggerated inflammatory responses |
| Antigen presentation & HLA molecules | Indirect presentation of donor antigens, T-cell anergy | Immune tolerance, potential link with tumor recurrence, alloimmunization |
| Innate–adaptive immune crosstalk | Neutrophil priming, monocyte/macrophage reprogramming, T-cell modulation | Immune imbalance → infection susceptibility, delayed healing, organ dysfunction |
| Blood Component | Key Mediators | Proposed Mechanisms | Clinical Consequences |
|---|---|---|---|
| Residual leukocytes (WBCs: monocytes, dendritic cells, lymphocytes, neutrophils) | MHC class II molecules (HLA-DR), alloantigens, cytokines | Antigen presentation leading to alloimmunization or T-cell anergy; microchimerism from donor cell persistence; apoptotic WBCs with phosphatidylserine exposure inducing immunosuppressive signaling | Alloimmunization, immune tolerance, microchimerism, TH2 shift, increased infection risk |
| Red blood cells (RBCs) | Hemolysis byproducts: free heme, iron, arginase, ATP, extracellular vesicles (EVs), residual mitochondria | Oxidative stress via ROS (Fenton chemistry); macrophage reprogramming (M1 vs. M2); ferroptosis and immune paralysis with iron overload; arginine depletion → reduced NO; ATP/adenosine signaling modulating innate/adaptive immunity; mitochondrial DNA as PAMPs | Inflammation, immune suppression, infections, sepsis, tumor growth, impaired vasodilation, alloimmunization |
| Platelets | Soluble CD40 ligand (sCD40L), platelet-derived EVs, microparticles, cytokines, chemokines, bioactive lipids | Immune cell activation (monocytes, T cells); endothelial activation; amplification of inflammatory cascades; delivery of procoagulant and proinflammatory EVs | Thrombosis, TRALI, systemic inflammation, immunosuppression in chronic transfusion |
| Plasma proteins | Soluble HLA molecules, microparticples, cytokines, anaphylatoxins (C3a, C5a), bioactive lipids | Modulation of innate/adaptive immunity; complement activation; induction of tolerance or inflammation depending on context | Infection risk, organ dysfunction, alloimmunization, anaphylactic reactions |
| Extracellular vesicles (from RBCs, platelets, WBCs) | MicroRNAs, proteins, oxidized phospholipids, mitochondrial fragments | Act as immune modulators by transferring bioactive molecules; neutrophil priming; endothelial activation; coagulation dysregulation | TRALI, systemic inflammation, microvascular injury, organ dysfunction |
| Storage lesion products (common to all cellular components) | Cytokines (IL-1, IL-6, IL-10, TNF-α), chemokines, oxidized lipids, free radicals | Accumulation during storage; trigger proinflammatory or immunosuppressive responses upon transfusion | Increased infection risk, inflammatory dysregulation, TRIM amplification |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Pérez-Calatayud, A.A.; Görlinger, K. Molecular Mechanisms of Transfusion-Associated Immunomodulation and Its Impact in the Critically Ill. Int. J. Mol. Sci. 2026, 27, 30. https://doi.org/10.3390/ijms27010030
Pérez-Calatayud AA, Görlinger K. Molecular Mechanisms of Transfusion-Associated Immunomodulation and Its Impact in the Critically Ill. International Journal of Molecular Sciences. 2026; 27(1):30. https://doi.org/10.3390/ijms27010030
Chicago/Turabian StylePérez-Calatayud, Angel Augusto, and Klaus Görlinger. 2026. "Molecular Mechanisms of Transfusion-Associated Immunomodulation and Its Impact in the Critically Ill" International Journal of Molecular Sciences 27, no. 1: 30. https://doi.org/10.3390/ijms27010030
APA StylePérez-Calatayud, A. A., & Görlinger, K. (2026). Molecular Mechanisms of Transfusion-Associated Immunomodulation and Its Impact in the Critically Ill. International Journal of Molecular Sciences, 27(1), 30. https://doi.org/10.3390/ijms27010030