


Abstract
Breaking up prolonged sitting with short bouts of light physical activity including standing and walking has been shown to be beneficial for people with type 2 diabetes (T2D). This paper presents the development of an android mobile app to deliver a just-in-time adaptive intervention (JITAI) to reduce sedentary time in people with T2D. A total of six design workshops were conducted with seven experts to identify design requirements, a behavioural framework, and required contextual adaptations for the development of a bespoke mobile app (iMOVE). Moreover, a focus group was conducted among people with T2D as potential end-users (N = 10) to ascertain their perceptions of the app. Feedback from the focus group was used in subsequent iterations of the iMOVE app. Data were analysed using an inductive qualitative thematic analysis. Based on workshops, key features of iMOVE were developed, including simplicity (e.g., navigation, login), colours and font sizes, push notifications, messaging algorithms, and a triggering system for breaking up sitting time and moving more. Based on the user testing results, a goal-setting tab was added, font sizes were made larger, the brightness of colours was reduced, and a colour indicator was used to indicate device connectivity with an activity tracker. A user-centric app was developed to support people with T2D to transition from sedentary to active lifestyles.
1. Introduction
Sedentary behaviour (SB) refers to any waking behaviour characterised by an energy expenditure of 1.5 or less metabolic equivalents (METs) while in a sitting, reclining, or lying posture [1]. Activity-tracking devices such as activPAL are used to measure SB and PA objectively [2,3]. Device-based data from the 2011–2012 Australian Diabetes, Obesity, and Lifestyle Study (AusDiab) showed that, on average, Australian adults spend 8.8 h per day sitting [2]. Using device-based measures of SB, it has been documented that people with type 2 diabetes (T2D) spend around 65% to 75% of their daily waking time being sedentary, which is higher than other population groups [3]. In addition to physical inactivity, excessive time spent sitting (whether sitting while doing nothing, using a computer or mobile, reading a book, or working on a desk) is now acknowledged as being a distinct risk factor for all-cause mortality and incidents of non-communicable diseases including T2D and cardiovascular disease [4]. Moreover, prolonged sitting among people with T2D is associated with poor glucose homeostasis [5]. SB adversely affects mental health outcomes including depression and cognitive function, as well as health-related quality of life [6].
Breaking up sitting time with activity is encouraged for maintaining good health in adults and older adults, including those with chronic conditions [7]. Interrupting sitting by standing and light walking has been shown to improve markers of cardiometabolic risk (e.g., insulin sensitivity, lipid profile, and diastolic blood pressure) in overweight adults [8]. In people with T2D, reducing and breaking up prolonged sitting time via light-intensity physical activity (e.g., slow walking) has been shown to improve glucose homeostasis and insulin sensitivity [5,9,10]. It is recommended for people with T2D to regularly break up their sitting time with activity in order to progress toward a more active lifestyle [11]. Recently, Dunstan and colleagues introduced the concept of a staircase approach for transitioning from SB to a more active lifestyle for cardiovascular health [12]. As a starting point to reduce overall sitting, this approach initially involves increasing standing and moving, followed by increasing light-intensity activity [12]. Sitting less and moving more can provide an important initial foundation for the longer-term transition to higher-intensity activity and improved cardiorespiratory fitness [12].
Digital health behaviour-change interventions have been shown to be effective in reducing SB [13]. Digital interventions using smartphones and wearable sensors (i.e., mHealth) offer unique opportunities for delivering interventions at more temporally salient moments and therefore maximise the potential opportunity for sustained behaviour change [14]. Referred to as just-in-time adaptive interventions or JITAIs, these interventions utilise collected data (i.e., sensor data) to adapt the components of the intervention to a person’s changing context (where) and status (when) [14,15]. In the context of PA and SB research, more evidence-based JITAIs are needed, including those informed by theory and effective behaviour-change techniques [16].
This paper describes the development of an android mobile application (iMOVE app) to deliver a JITAI aimed at reducing sitting time and increasing physical activity in people with T2D. For the proposed JITAI, a mobile app was required to connect to a wearable sensor (called SORD) to provide near/real time data on people’s SB and PA and to provide contextual information using smartphone sensors and Internet-connect information (e.g., GPS for location, weather forecast, accelerometers, etc.) [17]. Here, we describe the developmental stages of the iMOVE app. Specific aims include (1) to describe the user-interface including app content, data collection, wearable sensor integration, and theory and behavioural content; and (2) describe user-design with the target user group (adults with T2D).
2. Materials and Methods
2.1. Overview
A dual-stage qualitative study was conducted. Stage one consisted of interdisciplinary workshops among experts to discuss the requirements and to design a bespoke mobile app (iMOVE). An earlier systematic literature review by the authors of this study guided this stage [18]. Stage two involved a focus group with end-users and subsequent modifications of the app based on user feedback. Ethical clearance was granted by the Deakin University Human Research Ethics Committee (DUHREC).
2.2. Stage One: Designing iMOVE
A series of six workshops were conducted to develop a specification document for iMOVE, which included defining the design requirements (such as activity tracker, system, etc.), behavioural framework, and contextual adaptations (e.g., weather, etc.). An overview of topics discussed in the workshops is presented in Table 1. Workshops comprised study researchers (n = 7), including public health experts, exercise scientists, digital health experts, computer and information technology scientists, and engineers. In this phase, discussions were centred on app features, navigation and functionalities, aesthetics aspects (e.g., colours), and content, including framework and messages. Findings from our previous systematic review on JITAI identified the need to ensure push notifications from the app and include effective behaviour-change techniques (BCTs) to reduce SB and increase PA [18]. BCTs including behaviour substitution [19], social support [20], problem solving/barrier identification [20], instruction on how to perform the behaviour [19,21], providing information on the consequences of PA specific to the individual [20], prompts/cues [21], prompting generalization of a target behaviour [20], goal setting [20], self-monitoring [19], and feedback on behaviour [19] were found to fit with the JITAI concept of the current app. Using these BCTs, we then adapted relevant notification messages from the Direito et al. (2018) study [22].
Table 1.
Overview of the workshops to develop iMOVE.
2.3. Stage Two: Focus Group
The second stage involved an online focus group conducted via Zoom with people with T2D (N = 10). Participants were recruited via online advertisement on social media (Facebook and Instagram) among Australians. Participants were provided with a beta version of the iMOVE app to install on their mobile phones and provide feedback. Study researchers (BM & RD) used structured interview questions (see Supplementary File S1) to guide discussions. First, an introductory group discussion was conducted to obtain information about users’ past and current experience with health apps. Then, participants were asked to provide feedback about the functional features, aesthetic (i.e., look), and content of iMOVE. Moreover, participants were asked whether they were willing to have each feature on their own mobile phone. The app features were subsequently revised by the healthcare research and information technology team, based on findings from the focus group.
2.4. Analysis
For stage one, descriptive results were presented. For stage two, an inductive qualitative thematic analysis [23] was conducted. Sessions were recorded, transcribed verbatim, and analysed using NVivo 12 (QRS International Pty Ltd., Melbourne, VIC, Australia). Descriptive results were reported.
3. Results
3.1. Stage One
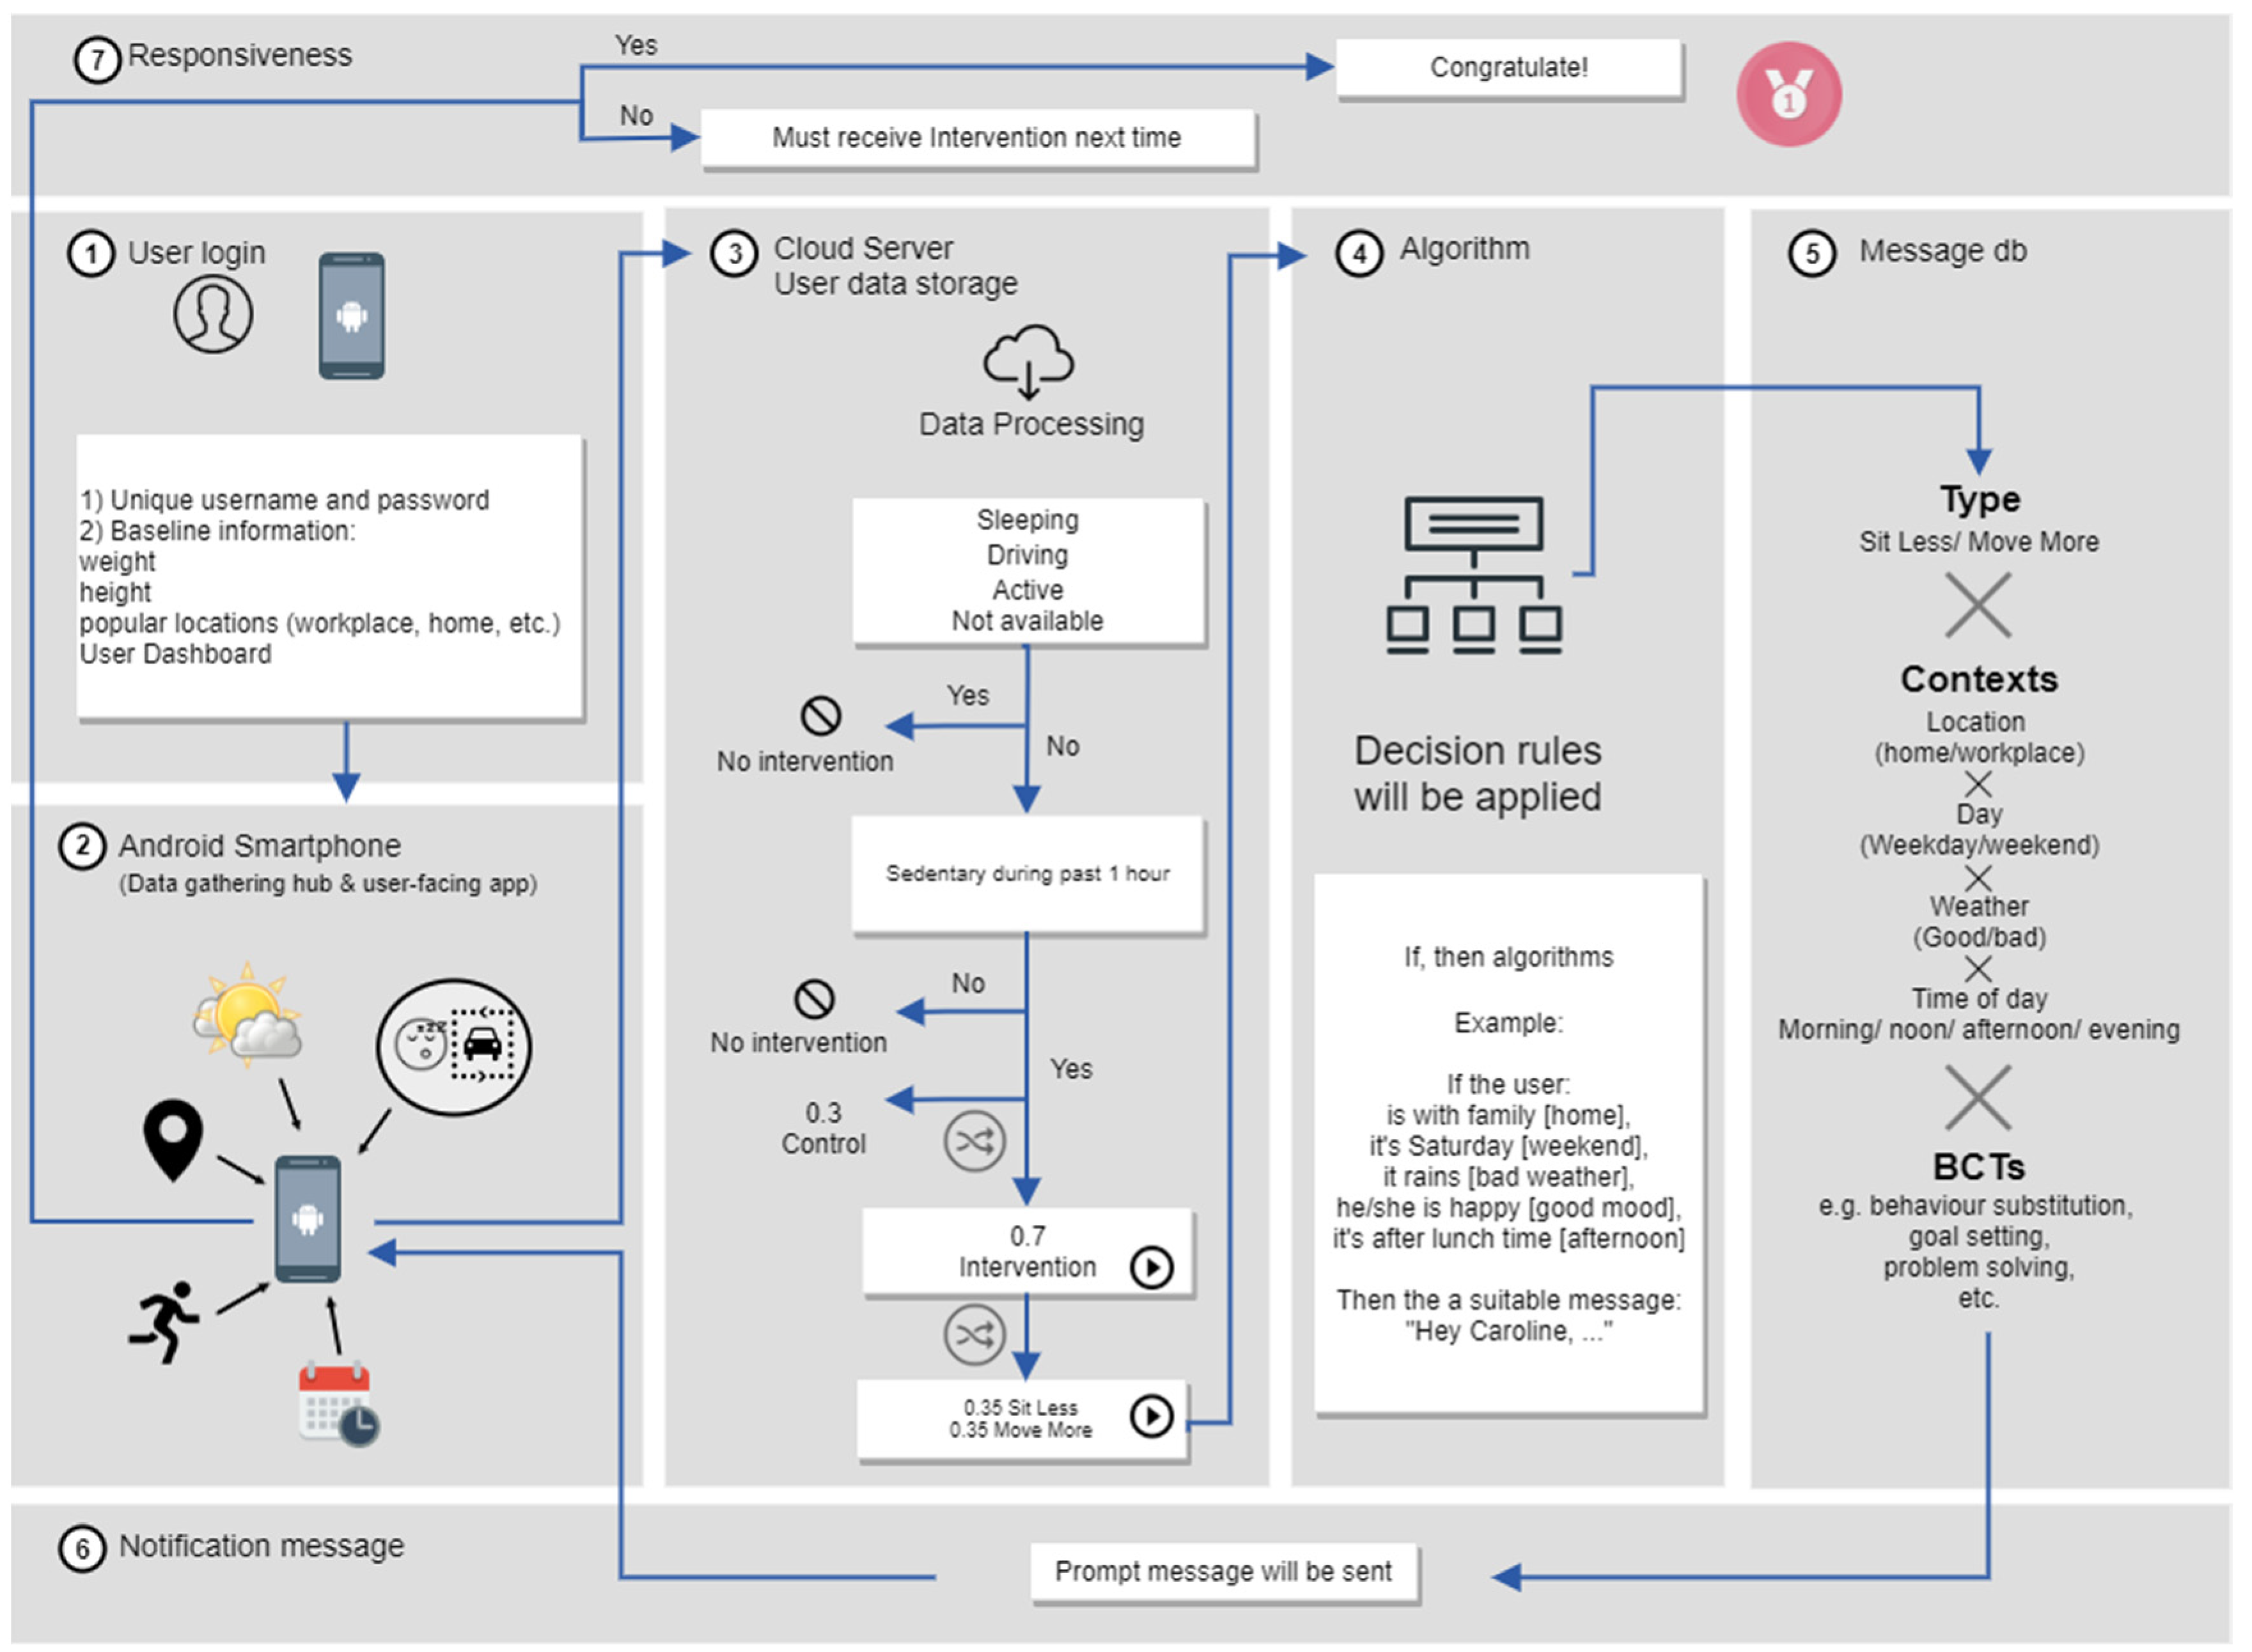
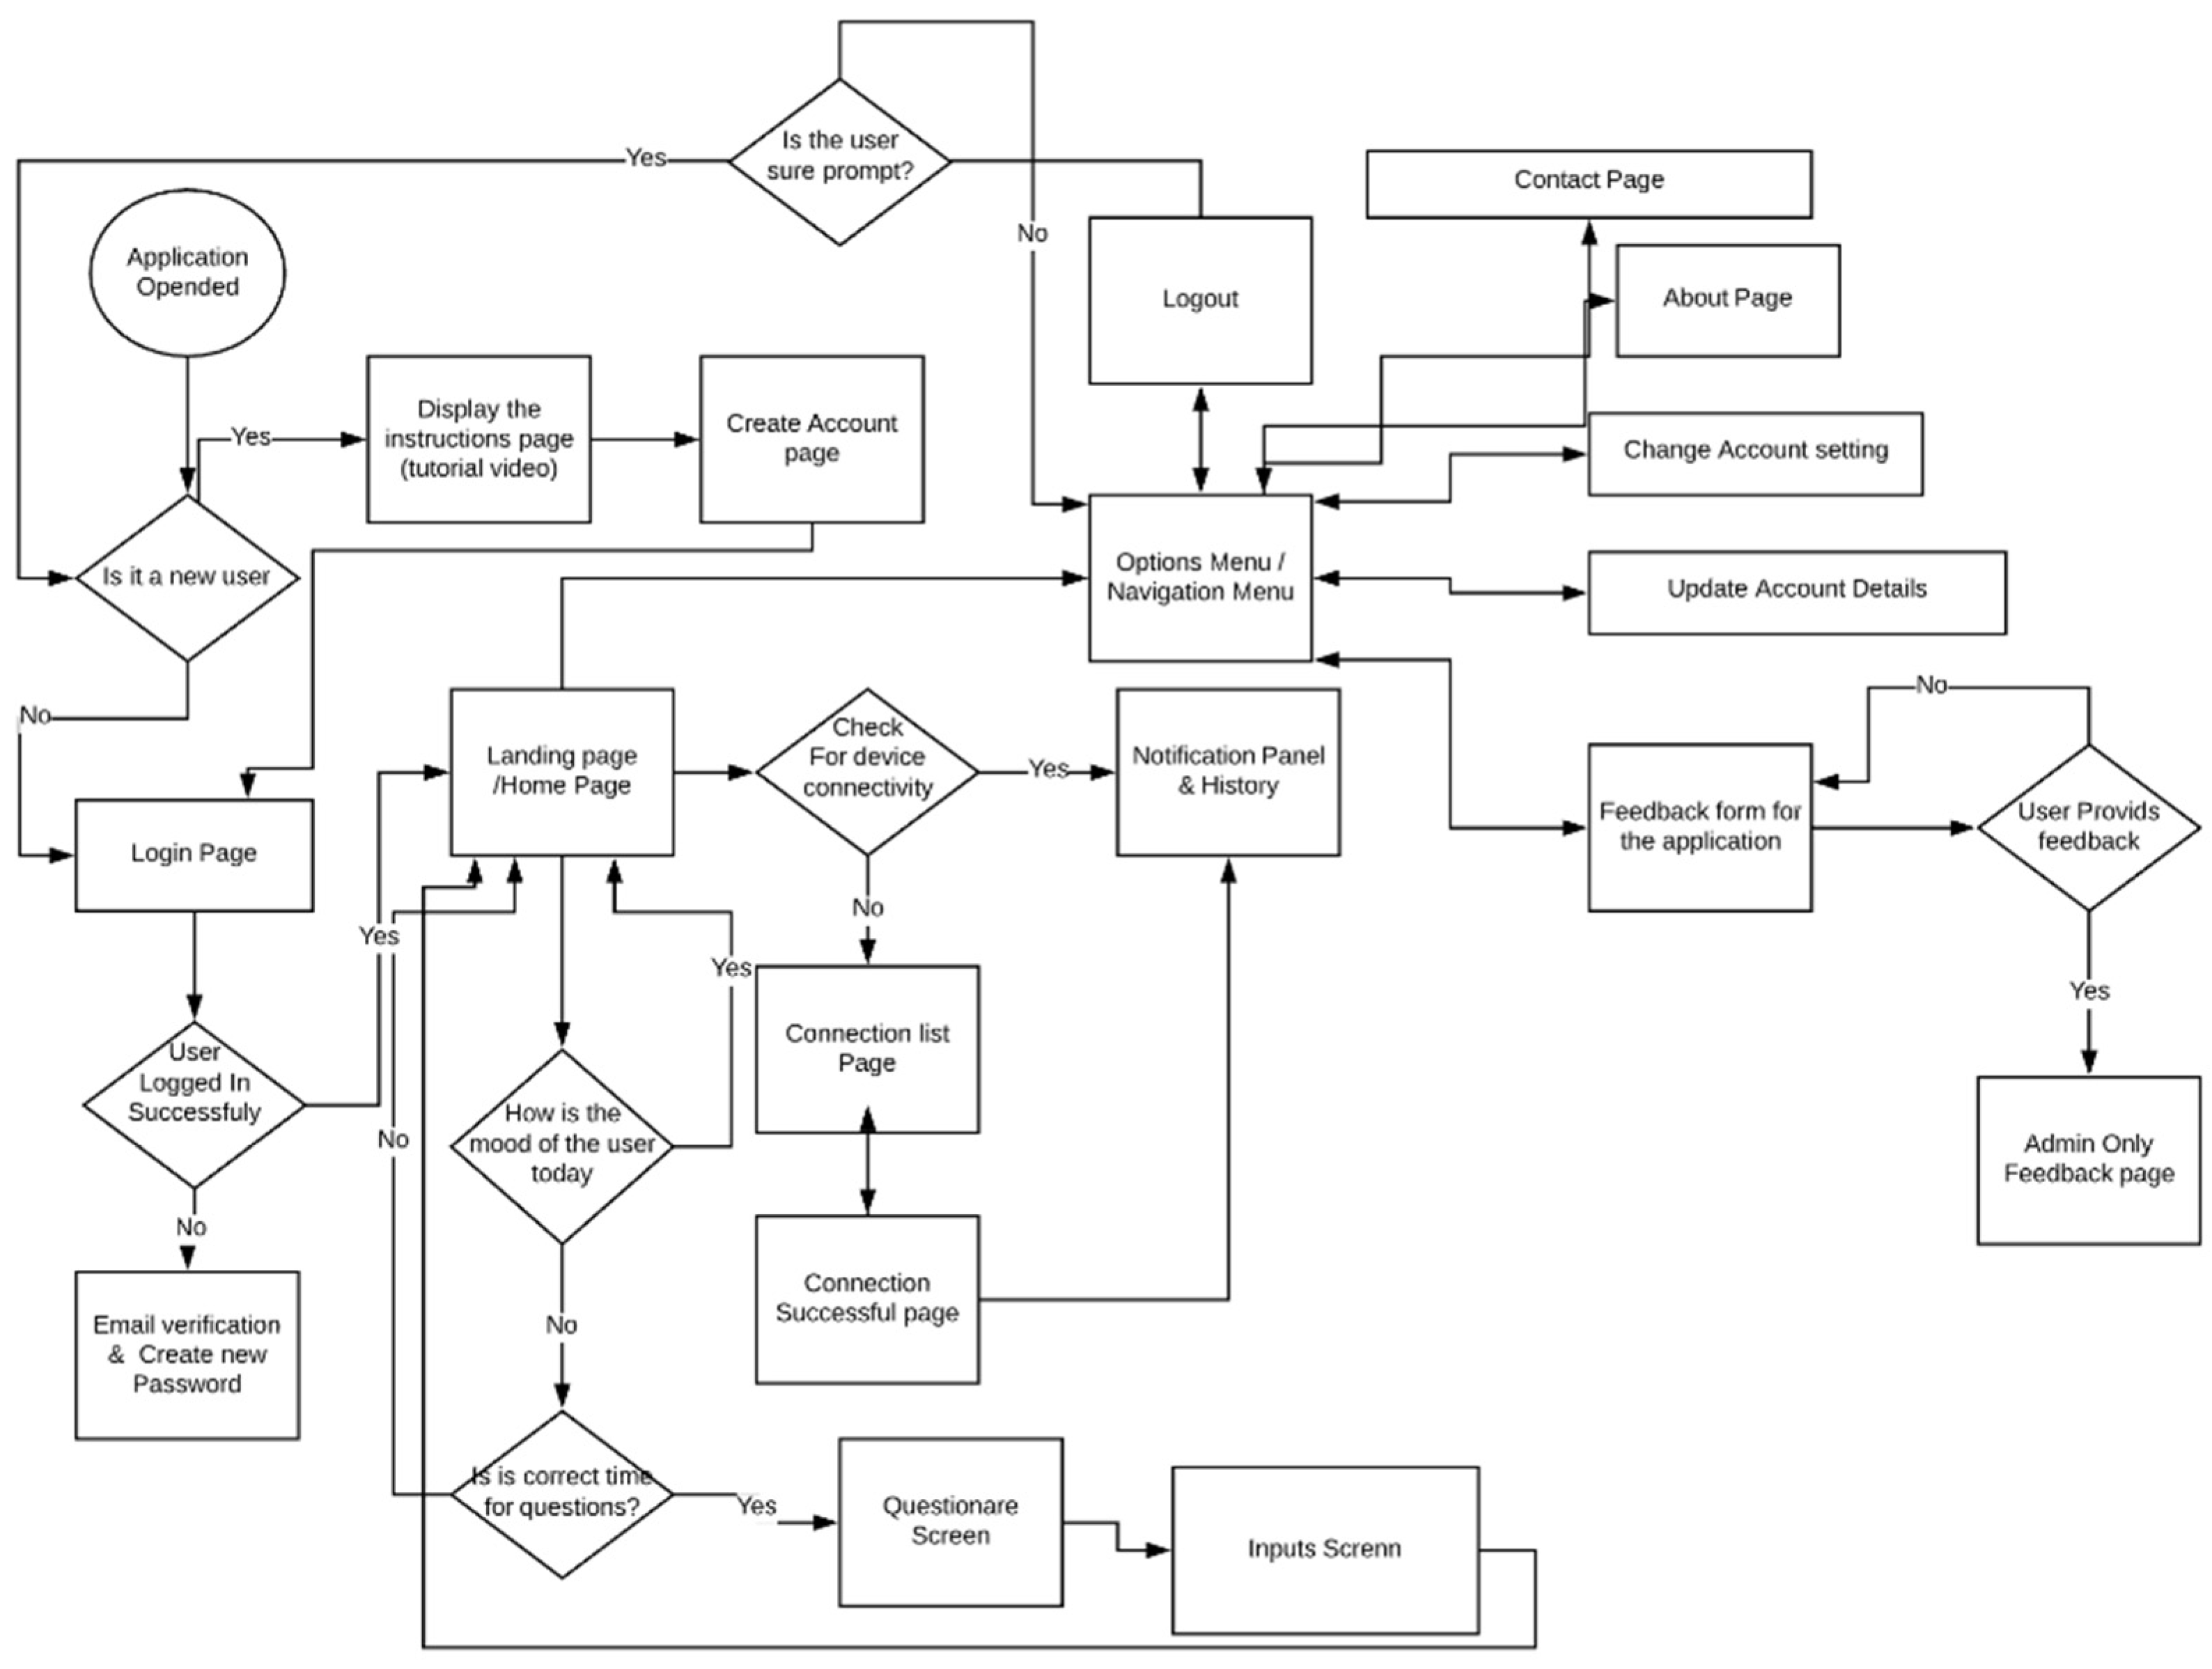
After agreeing on the app’s features, content, contextual information, and behavioural framework, the team ideated and created an app workflow (Figure 1). A logic flow was then created by the computer scientists for designing the backend, frontend, user interface, and machine learning algorithms (Figure 2). Based on the logic flow, the main features were specified, and then a mock-up was created using Adobe XD [24], a platform that enables designers to design the layout of the app pages while connecting these to navigation structure. At the end of stage 1, a beta version of the mobile app was designed.
Figure 1.
Workflow of the iMOVE app. db, database; BCTs, behaviour-change techniques.
Figure 2.
Logic flow of the iMOVE app.
3.1.1. App Features
Key findings from the design workshops included the need for the simple navigation of the app, with a limited number of tabs to scroll through. The iMOVE app required a Bluetooth connectivity function to connect with the SORD wearable sensor. Other features identified were the colours of the app, the registration and login structure, the security protocols, the need for a cloud server, data storage, messaging (or notification) algorithms, and a triggering system for delivering notifications. The workshops also discussed the feasibility of obtaining important contextual information, including location information obtained using the smartphone’s GPS, weather information using OpenWeather representational state transfer (REST) application programming interface (API) (London, UK), and time using Android LocalTime API. Based on the detailed specification document, we developed a Beta version of the app, which required 10 weeks for development. The Beta version was then utilised in Stage 2.
3.1.2. Notification Messages
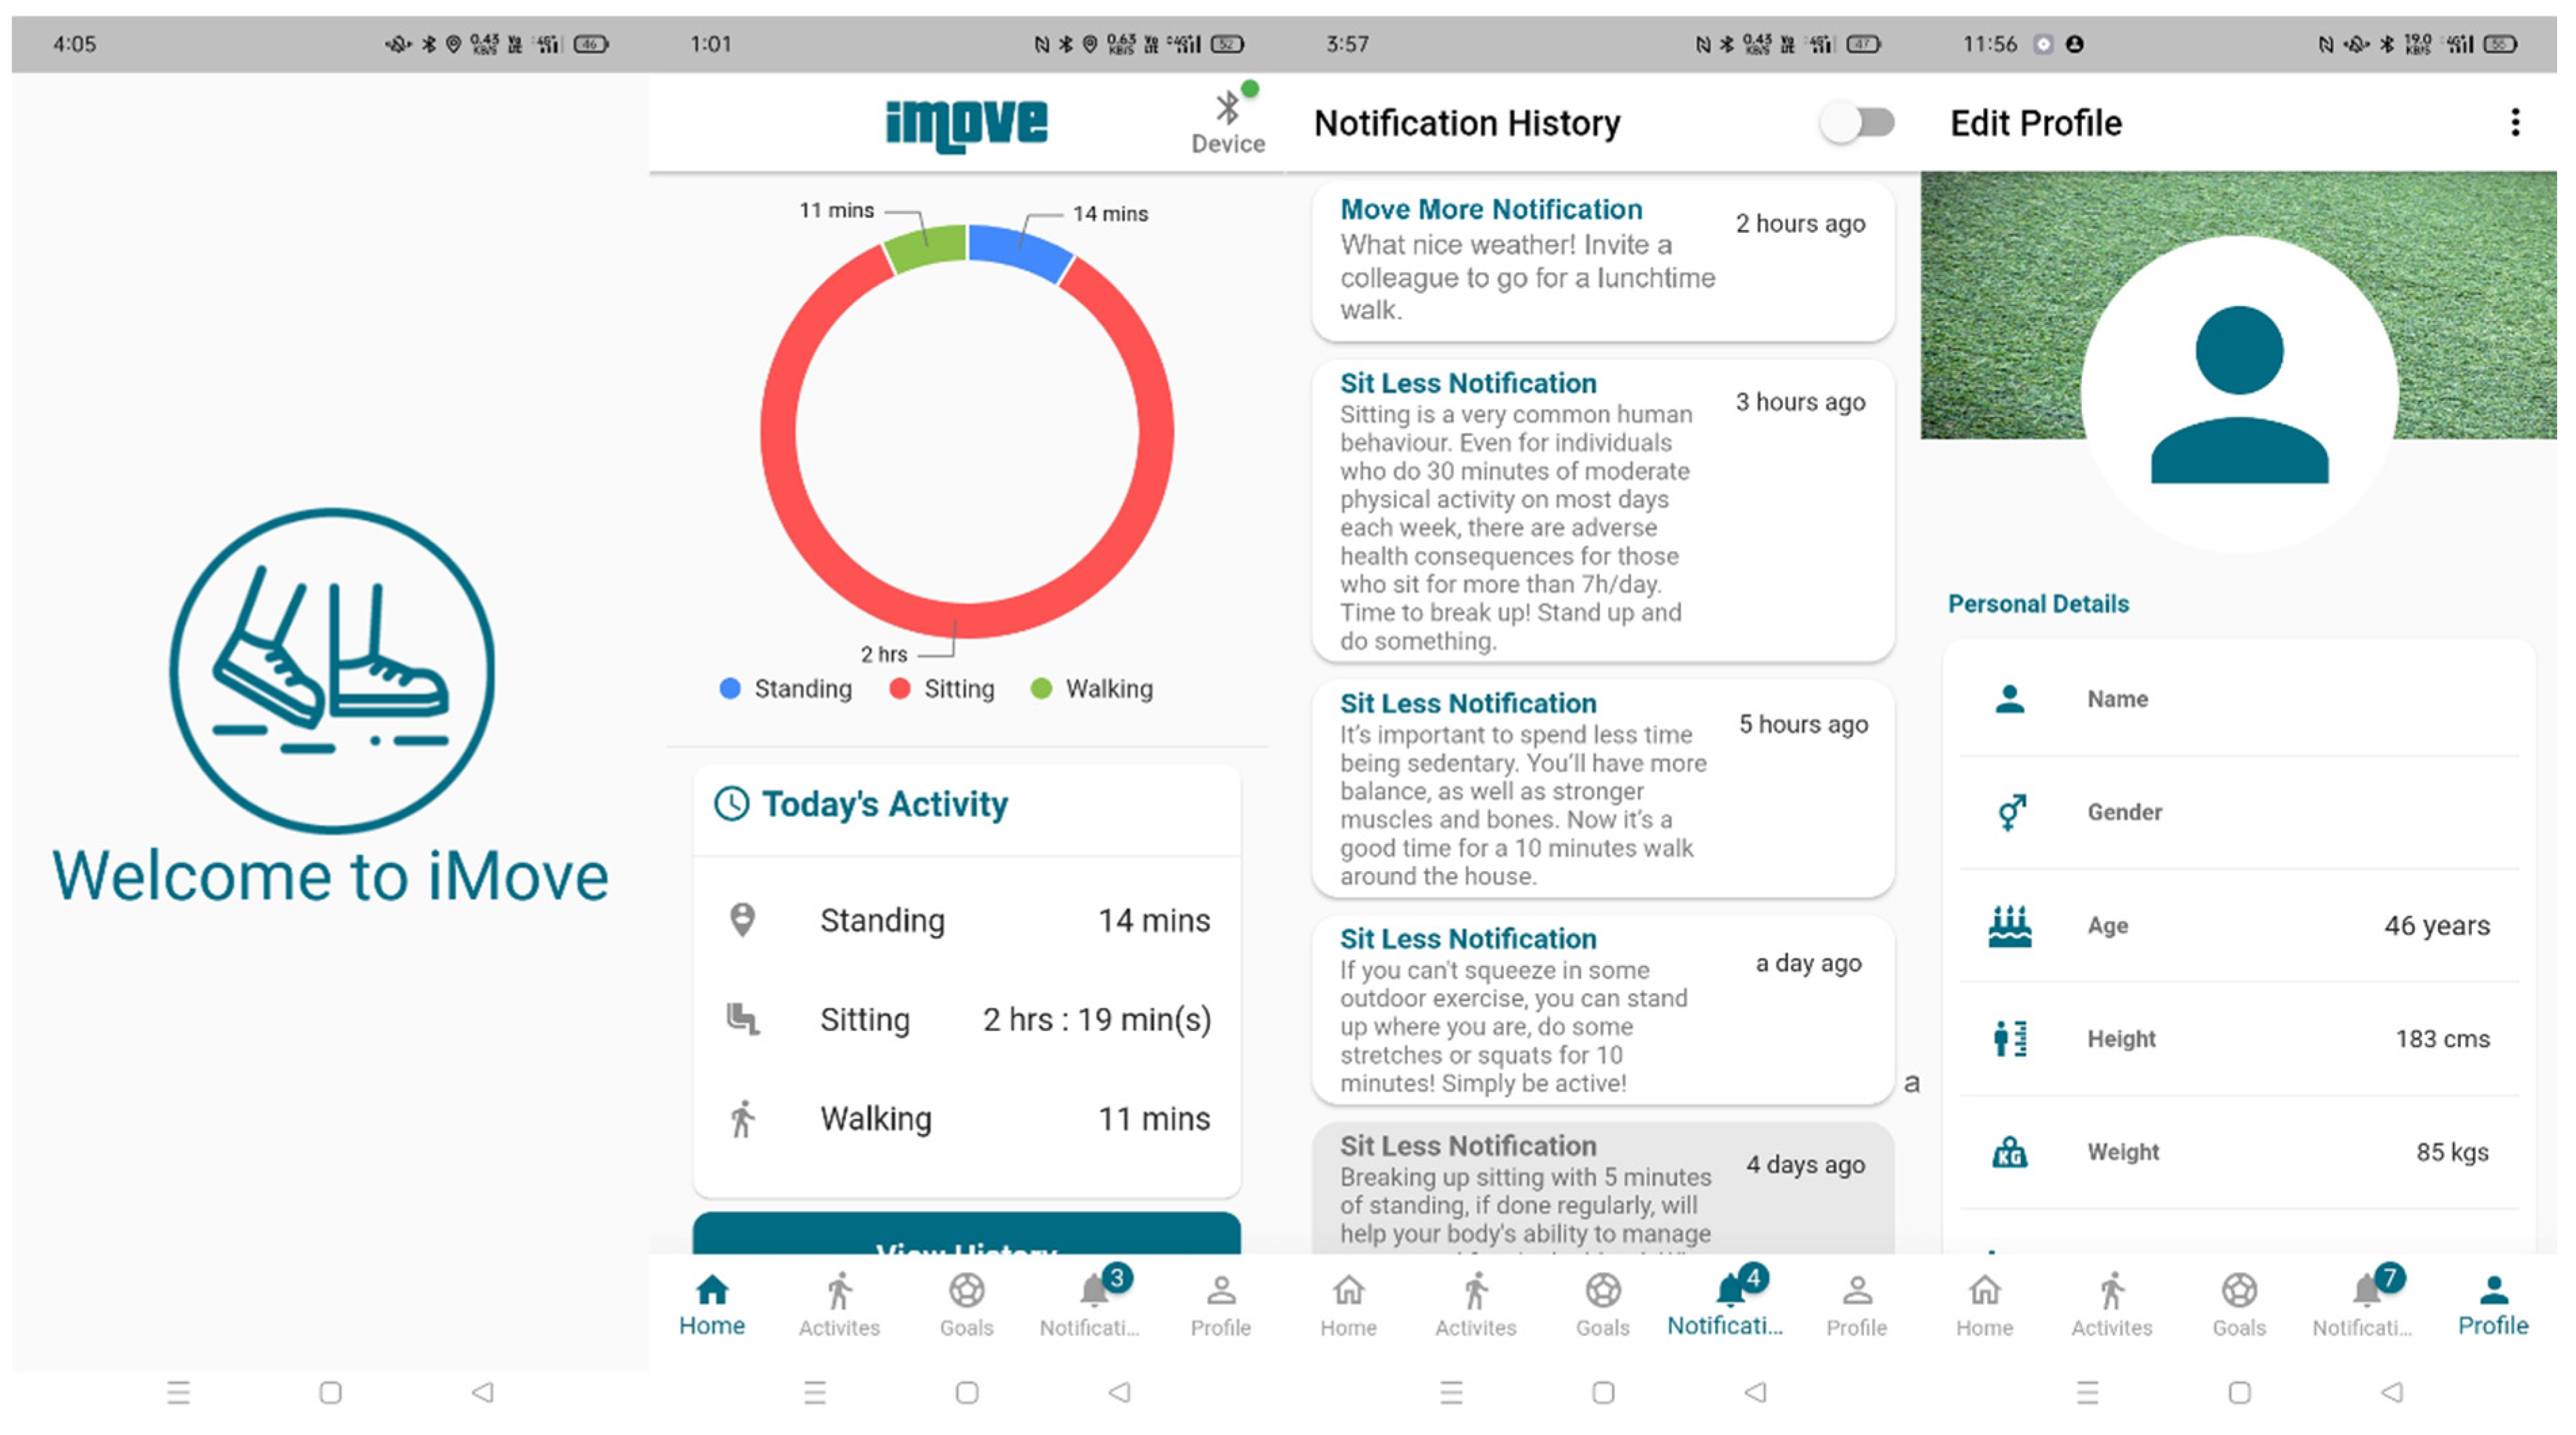
Two set of messages, including Sit Less and Move More, were created. Four researchers with content knowledge assessed the messages in terms of relevancy and clarity and provided feedback for improvement. Messages were further modified, then categorised into relevant contexts, and then transferred into a database (see Table S1 of Supplementary File S1 for example messages). A set of decision rules (algorithms) was defined for triggering micro-randomisation and intervention delivery at certain times and contexts (see Figure 3 for detailed example).
Figure 3.
iMOVE app images after modifications.
3.1.3. Wearable Sensor/Physical Activity Tracker Integration
Sedentary behaviOR Detector (SORD)—a prototype physical activity sensor, which was validated in a previous study [25]—was used to communicate with the iMOVE app for the real-time measurement of sitting, standing, and walking. It is noteworthy that iMOVE can potentially connect to the other third-party activity devices with Bluetooth capability, even though some minor backend work will be needed to implement the activity recognition of other devices.
3.2. Stage Two
Participants’ demographic information are presented in Table 2. The results of the focus group, including their experience with health apps; task-specific feedback about iMOVE; and feedback about aesthetic aspect, functional features, and content of iMOVE, are summarised in Table 3.
Table 2.
Demographic information of study participants.
Table 3.
Results of the iMOVE app focus group including domains, feedback (frequencies), and example quotes.
3.2.1. Past and Current Experience with Mobile Health Apps
Most participants liked apps that offered multifunctionality and included reminders (e.g., Samsung Health app). A tedious sign-up and sign-in process was disliked by most. Moreover, participants were concerned about their data privacy and felt their data were being sold to other companies.
3.2.2. General Feedback about iMOVE
Most participants liked the information on the home tab of iMOVE, which included a donut chart illustrating sitting, standing, and walking time for the current day and historically (see Figure 3). A majority of participants were concerned about their privacy regarding the personal information presented in the profile tab.
3.2.3. Aesthetic, Functional, and Content of iMOVE
Participants liked the overall colours and colour distinction in the donut chart; however, they thought some colours were too bright. Moreover, participants encountered problems in using the activity tab and found it unclear. Considering the functional aspects of iMOVE, most participants found the app easy to navigate but stated that the functionality of the Bluetooth icon was unclear. Most participants liked the intervention messages, especially the real-time nature of notifications.
3.2.4. Modifications
Based on the users’ feedback, potential modifications were further discussed with the research team, and decisions were made to iterate the iMOVE app. A goal-setting tab was added to the app to enable users to set personal weekly “Sit and Move goals”. General modifications involved increasing font size, reducing the brightness of colours, replacing the term “Bluetooth” with “Device”, and inserting colour indicators for the Bluetooth connectivity (red, not connected; green, connected). Further, technical issues were resolved “e.g., problems with select activity tab”, and some notes were added on the activity tab to guide users (e.g., “select date/time and activity here”). Date of birth was removed from the profile tab, and, instead, age was presented. See Figure 3 for the iMOVE app images after modifications.
4. Discussion
The purpose of this study was to describe the development of an Android mobile app for delivering a real-time and adaptive intervention to reduce sitting time and increase non-sitting time, i.e., standing and walking, among people with T2D. The initial selection of features for the iMOVE app was based on a review of the literature to deliver a JITAI, in addition to considering other features such as simplicity and aesthetic. The research team developed a basic app for delivering a JITAI and presented the app to the end-users for feedback. Overall, the app was found to be simple and useful by potential users. A few amenable areas and new essential features were identified (e.g., goal setting tab). The app and its content were revised based on the feedback on general, aesthetic, and functional aspects.
The iMOVE app is designed to help people transition from a sedentary to an active lifestyle by initially breaking up prolonged sitting time using activities such as standing or taking a short walk inside or outside the home. These are small yet significant changes in behaviour that can provide a preparation base for the individual to pursue further behaviour changes to achieve an activity goal. The available evidence has highlighted that apps are effective in reducing SB; however, there is scarcity of mobile apps for SB reduction among adults, including people with T2D [26]. Moreover, delivering JITAIs utilising either sensors or apps to reduce SB and promote PA is in its infancy [16]. It is argued that most JITAIs that have targeted PA are not truly adaptive and have used generic messages delivered at pre-set times [27].
Contextual information is important for providing more specificity on correlates of SB and PA, which will result in the better targeting of intervention [28]. Evidence suggests that variations in weather reduce the PA of people with T2D [29,30], and, therefore, accounting for weather in the interventions can help overcome this barrier. Strategies including adaptations to weather conditions (e.g., wearing tight clothing, short bouts of PA, etc.) and shifting to more indoor activities have been recommended for unfavourable weather conditions [31]. Moreover, in general, the PA level is higher during weekdays and lower in weekends among people with T2D [3], although individual responses may vary. Locations such as home and workplace are key environmental factors for determining PA [31]. Evidence suggests that location is the most important factor in receptiveness of SB intervention [28]. The iMOVE app uses GPS to tailor the intervention messages to the individual’s home and workplace locations.
Previous JITAIs developed in the context of PA and SB have lacked a theory basis, which is necessary to support behaviour change [16]. iMOVE app push messages were informed by a range of established BCTs to test the effectiveness of individual BCTs and generate new evidence.
Strength and Limitations
The strengths of the present study include a focus on both standing and moving to reduce SB. A prototype activity tracker enabled iMOVE to collect real-time data about standing in addition to sitting and walking. Testing iMOVE will generate new behavioural and contextual evidence about sitting and standing, as well as walking. A limitation of the study is the lack of mood assessment and inclusion in the contextual data collection. Psychological state, i.e., mood, was found to be associated with SB [32,33]. Another limitation is the adaptation of iMOVE intervention, which was limited to a number of settings (home and workplace) and did not include locations such as recreational sites and neighbourhood parks, etc. Moreover, we did not employ a full co-design methodology, which would have involved end-users from the beginning of the app’s development. Moreover, due to the online nature of the focus group, the users did not have a SORD device with them to check for connectivity. However, they could use the device-connectivity function and scan for devices. Finally, we did not conduct a formal face validity and usability test; however, participants provided feedback on the aesthetic and task-driven aspects of the app.
5. Conclusions
In this paper, the development of an android mobile app (iMOVE) to deliver a JITAI to reduce SB and increase PA among people with T2D is described. Based on a previous literature review and workshops among experts, a beta version of iMOVE was developed and presented to the end users with T2D. End-user feedback informed the improvement of iMOVE. This platform is designed to reduce prolonged sitting time in people with T2D and support them transition from a sedentary to a more active lifestyle. Future research will involve a micro randomised controlled trials to evaluate iMOVE in people living with T2D.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/electronics11193011/s1, Table S1. The interview questions for the stage 2 and examples of the intervention messages.
Author Contributions
R.D.-K.; R.M.; S.M.S.I.; D.W.D.; and M.A. designed the study and attended the workshops to discuss the design requirements. M.A. and T.P. programmed the app. R.D.-K. and B.M. conducted the focus group sessions. R.D.-K. performed the data analysis. R.D.-K. drafted the paper. All co-authors—R.M.; S.M.S.I.; D.W.D.; M.A.; and B.M.—contributed to the critical revision of the manuscript and approved the final manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This work was supported by Deakin University. R.D. received a Postgraduate Research Scholarship for his PhD from Deakin University.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Human Ethics Advisory Group of Deakin University (HEAG-H 224_2020).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The data presented in this study are available on request from the corresponding author. The data are not publicly available due to ethical mandates.
Acknowledgments
We would like to thank the Deakin Launchpad team and the Institute for Physical Activity and Nutrition (IPAN) at Deakin University for their support. We would also like to thank Zoe Wang for her assistance with app development.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Tremblay, M.S.; Aubert, S.; Barnes, J.D.; Saunders, T.J.; Carson, V.; Latimer-Cheung, A.E.; Chastin, S.F.; Altenburg, T.M.; Chinapaw, M.J. Sedentary behavior research network (SBRN)—Terminology consensus project process and outcome. Int. J. Behav. Nutr. Phys. Act. 2017, 14, 75. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Healy, G.N.; Winkler, E.A.; Owen, N.; Anuradha, S.; Dunstan, D.W. Replacing sitting time with standing or stepping: Associations with cardio-metabolic risk biomarkers. Eur. Heart J. 2015, 36, 2643–2649. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kennerly, A.M.; Kirk, A. Physical activity and sedentary behaviour of adults with type 2 diabetes: A systematic review. Pract. Diabetes 2018, 35, 86–89g. [Google Scholar] [CrossRef] [Scilit]
- Biswas, A.; Oh, P.I.; Faulkner, G.E.; Bajaj, R.R.; Silver, M.A.; Mitchell, M.S.; Alter, D.A. Sedentary time and its association with risk for disease incidence, mortality, and hospitalization in adults: A systematic review and meta-analysis. Ann. Intern. Med. 2015, 162, 123–132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Paing, A.C.; McMillan, K.A.; Kirk, A.F.; Collier, A.; Hewitt, A.; Chastin, S.F. The associations of sedentary time and breaks in sedentary time with 24-hour glycaemic control in type 2 diabetes. Prev. Med. Rep. 2018, 12, 94–100. [Google Scholar] [CrossRef] [Scilit]
- Saunders, T.J.; McIsaac, T.; Douillette, K.; Gaulton, N.; Hunter, S.; Rhodes, R.E.; Prince, S.A.; Carson, V.; Chaput, J.P.; Chastin, S.; et al. Sedentary behaviour and health in adults: An overview of systematic reviews. Appl. Physiol. Nutr. Metab. 2020, 45, S197–S217. [Google Scholar] [CrossRef] [Scilit]
- Bull, F.C.; Al-Ansari, S.S.; Biddle, S.; Borodulin, K.; Buman, M.P.; Cardon, G.; Carty, C.; Chaput, J.P.; Chastin, S.; Chou, R.; et al. World Health Organization 2020 guidelines on physical activity and sedentary behaviour. Br. J. Sports Med. 2020, 54, 1451–1462. [Google Scholar] [CrossRef] [Scilit]
- Duvivier, B.M.; Schaper, N.C.; Koster, A.; Van Kan, L.; Peters, H.P.; Adam, J.J.; Giesbrecht, T.; Kornips, E.; Hulsbosch, M.; Willems, P.; et al. Benefits of substituting sitting with standing and walking in free-living conditions for cardiometabolic risk markers, cognition and mood in overweight adults. Front. Physiol. 2017, 8, 353. [Google Scholar] [CrossRef] [Scilit]
- Dempsey, P.C.; Owen, N.; Yates, T.E.; Kingwell, B.A.; Dunstan, D.W. Sitting less and moving more: Improved glycaemic control for type 2 diabetes prevention and management. Curr. Diabetes Rep. 2016, 16, 114. [Google Scholar] [CrossRef] [Scilit]
- Duvivier, B.M.; Schaper, N.C.; Hesselink, M.K.; van Kan, L.; Stienen, N.; Winkens, B.; Koster, A.; Savelberg, H.H. Breaking sitting with light activities vs structured exercise: A randomised crossover study demonstrating benefits for glycaemic control and insulin sensitivity in type 2 diabetes. Diabetologia 2017, 60, 490–498. [Google Scholar] [CrossRef] [Scilit]
- Dempsey, P.C.; Owen, N.; Biddle, S.J.; Dunstan, D.W. Managing sedentary behavior to reduce the risk of diabetes and cardiovascular disease. Curr. Diabetes Rep. 2014, 14, 522. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dunstan, D.W.; Dogra, S.; Carter, S.E.; Owen, N. Sit less and move more for cardiovascular health: Emerging insights and opportunities. Nat. Rev. Cardiol. 2021, 18, 637–648. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stephenson, A.; McDonough, S.M.; Murphy, M.H.; Nugent, C.D.; Mair, J.L. Using computer, mobile and wearable technology enhanced interventions to reduce sedentary behaviour: A systematic review and meta-analysis. Int. J. Behav. Nutr. Phys. Act. 2017, 14, 105. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Spruijt-Metz, D.; Wen, C.K.; O’Reilly, G.; Li, M.; Lee, S.; Emken, B.A.; Mitra, U.; Annavaram, M.; Ragusa, G.; Narayanan, S. Innovations in the use of interactive technology to support weight management. Curr. Obes. Rep. 2015, 4, 510–519. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Intille, S.S.; Kukla, C.; Farzanfar, R.; Bakr, W. Just-in-time technology to encourage incremental, dietary behavior change. AMIA Annu. Symp. Proc. 2003, 2003, 874. [Google Scholar]
- Hardeman, W.; Houghton, J.; Lane, K.; Jones, A.; Naughton, F. A systematic review of just-in-time adaptive interventions (JITAIs) to promote physical activity. Int. J. Behav. Nutr. Phys. Act. 2019, 16, 31. [Google Scholar] [CrossRef] [Scilit]
- Brusse, C.; Gardner, K.; McAullay, D.; Dowden, M. Social media and mobile apps for health promotion in Australian Indigenous populations: Scoping review. J. Med. Internet Res. 2014, 16, e280. [Google Scholar] [CrossRef] [Scilit]
- Schwarz, D. Jump Start Adobe XD; SitePoint: Melbourne, Australia, 2017. [Google Scholar]
- Willig, C.; Rogers, W.S. The SAGE Handbook of Qualitative Research in Psychology; Sage: New York, NY, USA, 2017. [Google Scholar]
- Daryabeygi-Khotbehsara, R.; Islam, S.M.S.; Dunstan, D.; McVicar, J.; Abdelrazek, M.; Maddison, R. Smartphone-based interventions to reduce sedentary behavior and promote physical activity using integrated dynamic models: Systematic review. J. Med. Internet Res. 2021, 23, e26315. [Google Scholar] [CrossRef] [Scilit]
- Gardner, B.; Smith, L.; Lorencatto, F.; Hamer, M.; Biddle, S.J. How to reduce sitting time? A review of behaviour change strategies used in sedentary behaviour reduction interventions among adults. Health Psychol. Rev. 2016, 10, 89–112. [Google Scholar] [CrossRef] [Scilit]
- Direito, A.; Walsh, D.; Hinbarji, M.; Albatal, R.; Tooley, M.; Whittaker, R.; Maddison, R. Using the Intervention Mapping and Behavioral Intervention Technology Frameworks: Development of an mHealth Intervention for Physical Activity and Sedentary Behavior Change. Health Educ. Behav. 2018, 45, 331–348. [Google Scholar] [CrossRef] [Scilit]
- Avery, L.; Flynn, D.; Van Wersch, A.; Sniehotta, F.F.; Trenell, M.I. Changing physical activity behavior in type 2 diabetes: A systematic review and meta-analysis of behavioral interventions. Diabetes Care 2012, 35, 2681–2689. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Howlett, N.; Trivedi, D.; Troop, N.A.; Chater, A.M. Are physical activity interventions for healthy inactive adults effective in promoting behavior change and maintenance, and which behavior change techniques are effective? A systematic review and meta-analysis. Transl. Behav. Med. 2019, 9, 147–157. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daryabeygi-Khotbehsara, R.; Rawstorn, J.; Shariful Islam, S.M.; Dunstan, D.W.; Abdelrazek, M.; Kouzani, A.; Thummala, P.; McVicar, J.; Maddison, R. Validation of a Bluetooth-enabled Device for Real-time Detection of Sitting, Standing and Walking. J. Sports Sci. 2022. under-review. [Google Scholar]
- Ueno, D.T.; Guerra, P.H.; Christofoletti, A.E.M.; Bonolo, A.; Nakamura, P.M.; Kokubun, E. Mobile health apps to reduce sedentary behavior: A scoping review. Health Promot. Int. 2022, 37, daab124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saponaro, M.; Vemuri, A.; Dominick, G.; Decker, K. Contextualization and individualization for just-in-time adaptive interventions to reduce sedentary behavior. In Proceedings of the Conference on Health, Inference, and Learning, Virtual Event, 8–10 April 2021. [Google Scholar]
- Loveday, A.; Sherar, L.B.; Sanders, J.P.; Sanderson, P.W.; Esliger, D.W. Novel technology to help understand the context of physical activity and sedentary behaviour. Physiol. Meas. 2016, 37, 1834–1851. [Google Scholar] [CrossRef] [Scilit]
- Dasgupta, K.; Chan, C.; Da Costa, D.; Pilote, L.; De Civita, M.; Ross, N.; Strachan, I.; Sigal, R.; Joseph, L. Walking behaviour and glycemic control in type 2 diabetes: Seasonal and gender differences-Study design and methods. Cardiovasc. Diabetol. 2007, 6, 1–11. [Google Scholar] [CrossRef] [Scilit]
- Dasgupta, K.; Joseph, L.; Pilote, L.; Strachan, I.; Sigal, R.J.; Chan, C. Daily steps are low year-round and dip lower in fall/winter: Findings from a longitudinal diabetes cohort. Cardiovasc. Diabetol. 2010, 9, 81. [Google Scholar] [CrossRef] [Scilit]
- Kelso, A.; Reimers, A.K.; Abu-Omar, K.; Wunsch, K.; Niessner, C.; Wäsche, H.; Demetriou, Y. Locations of physical activity: Where are children, adolescents, and adults physically active? A systematic review. Int. J. Environ. Res. Public Health 2021, 18, 1240. [Google Scholar] [CrossRef] [Scilit]
- Richter, M. The association between Sedentary Time, Physical Activity and Mood: An Experience Sampling Study. Bachelor’s Thesis, University of Twente, Enschede, The Netherlands, 2021. [Google Scholar]
- Yoshiuchi, K.; Nakahara, R.; Kumano, H.; Kuboki, T.; Togo, F.; Watanabe, E.; Yasunaga, A.; Park, H.; Shephard, R.J.; Aoyagi, Y. Yearlong physical activity and depressive symptoms in older Japanese adults: Cross-sectional data from the Nakanojo study. Am. J. Geriatr. Psychiatry 2006, 14, 621–624. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).