


Abstract
Multiple sclerosis (MS) is an autoimmune disease of the central nervous system and is considered to be the leading non-traumatic cause of neurological disability in young adults. Current treatments for MS comprise long-term immunosuppressant drugs and disease-modifying therapies (DMTs) designed to alter its progress with the enhanced risk of severe side effects. The Holy Grail for the treatment of MS is to specifically suppress the disease while at the same time allow the immune system to be functionally active against infectious diseases and malignancy. This could be achieved via the development of immunotherapies designed to specifically suppress immune responses to self-antigens (e.g., myelin antigens). The present study attempts to highlight the various antigen-specific immunotherapies developed so far for the treatment of multiple sclerosis (e.g., vaccination with myelin-derived peptides/proteins, plasmid DNA encoding myelin epitopes, tolerogenic dendritic cells pulsed with encephalitogenic epitopes of myelin proteins, attenuated autologous T cells specific for myelin antigens, T cell receptor peptides, carriers loaded/conjugated with myelin immunodominant peptides, etc.), focusing on the outcome of their recent preclinical and clinical evaluation, and to shed light on the mechanisms involved in the immunopathogenesis and treatment of multiple sclerosis.
1. Introduction
Multiple sclerosis (MS) is a chronic inflammatory disease of the central nervous system (CNS) caused by genetically-predisposed hosts by infectious and environmental factors which induce complex autoimmune responses in the CNS resulting in degeneration of the myelin sheath and axonal loss in the brain and spinal cord [1,2,3,4,5,6,7,8,9,10,11,12,13,14] It is the most prominent demyelinating disease leading to progressive clinical disability in MS patients [5,6,15] due to ineffective remyelination [13,15]. More than 2 million people worldwide suffer from MS and it is considered as the leading non-traumatic cause of neurological disability in young adults with a disease onset commonly around 20 and 40 years of age [4,6,15,16]. High prevalence of the disease is reported in North America and Europe [15].
MS exhibits a vastly heterogeneous clinical course [6,17] which varies from a benign disease course that doesn’t lead to serious disability, demonstrated by 10–15% of MS patients, to aggressive forms of the disease leading to severe disability and even paralysis. The increased heterogeneity of the disease severity strongly affects the design and duration of therapeutic schemes administered to MS patients [17].
MS features the following stages: a pre-clinical stage, namely, a radiologically-isolated syndrome (RIS), which is then demonstrated as a clinically-isolated syndrome (CIS) [2,3], followed by a relapsing remitting stage (RRMS) which may later advance into secondary progressive disease (SPMS) [2,4,6,16,18]. It should be noted that a minority of MS patients (e.g., 10–15% [3,6,16]) exhibit progressive MS from the disease onset, known as primary progressive MS (PPMS) [2,4,6,18] (Figure 1). The aforementioned classification corresponds to the inflammatory image of MS which can be detected via magnetic resonance imaging (MRI) [2,16].
Figure 1.
Stages of multiple sclerosis (MS). RIS: radiologically isolated syndrome; CIS: clinically isolated syndrome; FDA: U.S. food and drug administration (with the permission of [2]).
RRMS affects approximately 85% of MS patients [3,6,19] of whom women are twice as many as men [6]. It is characterized by periods of relapses (i.e., episodes of neurologic dysfunction, such as sensory disturbances, optic neuritis, or disturbances of motor/cerebellar function) followed by remission periods (i.e., periods of partial or full clinical recovery) [2,3,6,14,16]. Relapses coincide with CNS inflammation/demyelination visualized by MRI as lesions found mainly in the white matter [3]. In the majority of patients, RRMS advances to SPMS [16] within 10–20 years after diagnosis [3,6].
RRMS involves the movement of immune cells from the peripheral sites to the CNS (mainly in the white matter, even though extensive number of demyelinated plaques can be located in the grey matter [20]) resulting in the formation of localized inflammatory sites. Inflammatory processes in these sites induce killing of oligodendrocytes, myelin damage, and axon injury and loss, resulting in impaired neurological function [20]. On the other hand, the progressive disease implicates the generation of a pathological process within the brain [2]. Thus, the characteristic feature of SPMS is no longer the inflammatory lesions but an atrophic brain attributed to enhanced loss of axons, cortical demyelination, activation of microglia, and inefficient remyelination [2,3]. SPMS patients demonstrate progressive neurological dysfunction resulting in enhanced physical disability (e.g., inability to walk) [2,3].
PPMS is also characterized by gradual neurological decline without relapses [3,6]. In comparison with RRMS, the disease onset for PPMS is usually ten years later and it does not exhibit female predominance [6]. To date, clinical evidence shows significant differences between RRMS and progressive MS [21], reflected by the diverse response to currently existing treatments, but not between SPMS and PPMS. [18].
Currently, there is no cure for MS. Some existing treatments appear to be beneficial for patients with RRMS. However, there is still a lack of effective therapies for the progressive forms of MS [2].
The present paper aims to extensively review the different, recently developed myelin antigen-specific strategies (e.g., myelin peptide based vaccination, vaccination with plasmid DNA encoding myelin epitopes, tolerogenic dendritic cells pulsed with encephalitogenic epitopes of myelin proteins, vaccination with attenuated autologous T cells specific for myelin antigens, T cell receptor vaccination, carrier-aided administration of myelin immunodominant peptides, etc.) for the prevention/treatment of MS, especially with respect to their in vivo and clinical evaluation outcomes and the challenges they face in order to be translated to MS patients. It also seeks to unravel the mechanisms involved in the immunopathogenesis of the relapsing remitting and progressive MS, as well as the mechanisms of action of the developed tolerance-inducing vaccines.
The different antigen-specific immunotherapies are analytically presented in a comparative manner in separate tables providing detailed information about the selected myelin antigen, the vaccination strategy (e.g., prophylactic, preclinical, therapeutic), the administration route (e.g., intravenous, subcutaneous, intraperitoneal, epicutaneous, intradermal, oral, nasal, pulmonary) and the administered dose, the cell type (e.g., tolerogenic dendritic cells, T cells, hematopoietic stem cells, bone marrow cells) and the inductive agent, the carrier type (e.g., polymer particles, soluble antigen arrays, immune polyelectrolyte multilayers, inorganic particles, pMHC-NPs, mannan-conjugated myelin peptides, liposomes, exosomes, antigen-presenting yeast cells), and its characteristics (e.g., size, zeta potential, antigen loading), as well as the vaccination outcome.
The review paper is based on a systematic search of PubMed using the following search terms: multiple sclerosis, antigen-specific immunotherapies, tolerogenic vaccines, nanocarriers, nanomedicine, DNA vaccination, cell-based vaccination, clinical trials. The search covered the time period from 1 January 2000 till today. Publications addressing pre-clinical and clinical evaluation of antigen-specific immunotherapies for multiple sclerosis were selected for inclusion.
2. Immunopathogenesis of MS
Successful preclinical studies and clinical trials for MS which target cells and molecules of the immune system support the idea that the latter has a dominant role in the pathogenesis of MS. These studies have proposed that cells of the adaptive immune system like B cells and various effector T cells, combined with cells of the innate immune system such as natural killer cells and microglia, uniquely contribute to the disease [2]. However, it should be mentioned that while the peripheral adaptive immune system (T lymphocytes) is the primary driver of RRMS, the innate immune system (microglia and astrocytes) together with B lymphocytes is considered to drive progressive MS [2]. The CNS of MS patients has been also found to exhibit infiltration of activated T cells, B cells, plasma cells, dendritic cells (DCs), and macrophages indicating the contribution of both cellular and humoral (i.e., antibody-mediated) immune responses as well as of various immunopathological effector mechanisms to the damage of CNS tissue [22,23].
It has been suggested that two independent types of inflammation, developing in parallel, can occur in multiple sclerosis patients. The first one is related with the focal invasion of T and B cells through BBB leakage, giving rise to classic active demyelinated plaques in the white matter. The second one deals with a slow accumulation of T and B lymphocytes without profound BBB damage in the perivascular Virchow Robin spaces and the meninges, where they form cellular aggregates resembling, in most severe cases, tertiary lymph follicles. The latter can be linked with the development of demyelinated lesions in the cerebral and cerebellar cortex, slow expansion of existing lesions in the white matter, and diffuse neurodegeneration in normal-appearing white and/or grey matter [18]. The presence of the lymphoid follicle-like structures (follicle-like ectopic germinal centers) in the inflamed cerebral meninges of some SPMS patients could indicate that B-cell maturation is sustained locally in the CNS and contributes to the induction of a compartmentalized humoral immune response [2,22].
The role of the various immune cells and the immunopathological effector mechanisms contributing to the development of MS are discussed below.
The ability of the human immune system to respond to an enormous number of encountered antigens comes with the risk that some T cells will be able to recognize self-antigens, such as CNS (e.g., myelin) antigens. Most autoreactive T lymphocytes are usually deleted in the thymus via a process known as negative selection (central tolerance). However, a number of these T cells escape from the thymus to peripheral sites where they are normally kept under control by mechanisms of peripheral tolerance. If these mechanisms fail, due to reduced action of regulatory T cells and/or enhanced resistance of effector T and B lymphocytes to suppression, autoreactive T cells recognizing CNS antigens are activated in the peripheral lymphoid system to become effector cells, via molecular mimicry (i.e., activation by a viral peptide having sufficient sequence similarity [24] or otherwise sharing an immunologic epitope [25] with the CNS antigen), recognition of CNS proteins released in the periphery, presentation of new autoantigens and bystander activation (i.e., T cell receptor (TCR)-independent and cytokine-dependent activation probably due to viral infection [26]). Then the activated T cells (CD8+ T cells, and CD4+ T cells differentiate to T helper 1 (Th1) and Th17 cells) together with B cells and monocytes (cells of the innate immune system) infiltrate the CNS by crossing the blood-brain barrier (BBB) leading to inflammation. There, they are reactivated via encountered resident antigen presenting cells, APCs (e.g., microglial cells) and infiltrating APCs (e.g., dendritic cells, macrophages) presenting CNS autoantigens on the major histocompatibility complex, MHC (also known as human leucocyte antigen, HLA, in humans [11]) molecules. Specifically, CD4+ T cells interact with MHC II expressing cells, like dendritic cells, macrophages and B cells, whereas CD8+ T cells directly interact with MHC I/antigen-expressing cells, like neurons and oligodendrocytes. It should be noted that MHC class II is adequately expressed only on professional APCs, while MHC class I is expressed by all cell types in the CNS inflammatory milieu. Therefore, CD4+ T cells are mainly found in perivascular cuffs, and meninges, whereas CD8+ T cells additionally infiltrate the parenchyma of the irritated lesions. Upon contact with their cognate antigen, CD4+ T cells are thought to secrete cytokines and immune mediators resulting in the attraction of resident immune cells like microglia, macrophages and astrocytes, secretion of proinflammatory cytokines, enhanced APC function, and increased production of reactive oxygen and nitrogen species (ROS/RNS). On the other hand, apart from secreting inflammatory mediators, CD8+ T cells directly attack oligodendrocytes and neurons, thus causing oligodendrocyte death (e.g., via secretion of granzymes and perforin leading to pore formation and stimulation of programmed cell death [2]) and neuronal damage (e.g., release of cytolytic granules leading to axonal dissection [2]) (Figure 2). The above result in inflammation, myelin loss, and axonal injury. This inflammatory cascade leads to the recruitment of monocytes and macrophages into the lesion resulting in the release of more CNS antigens and their presentation to potentially autoreactive T cells. It should be mentioned that epitope spreading could result in a broader autoimmune response involving additional autoantigens [1,2,3,11,27,28,29,30,31,32,33].
Figure 2.
Effector T cells in multiple sclerosis (with the permission of [2]).
CD4+ T cells are considered to have a paramount role in the immunopathogenesis of MS due to the secretion of interferon gamma (IFNγ) and IL-17 [2,20,34]. However, it has been lately revealed that CD8+ T cells are also responsible for the initiation of human MS pathogenesis where, contrary to experimental autoimune encephalomyelitis (EAE), CD8+ T cells are the predominant T lymphocyte infiltrate in acute and chronic MS lesions [1,2]. Compared with CD4+ T cells, CD8+ T cells can be found more frequently in the white matter and in the cortical demyelinating lesions in the grey matter, and their density can be closely correlated with axonal damage [1,3]. Epitope spreading, assisted by cross-presentation of antigens by monocyte-derived DCs, has been found to activate myelin-specific CD8+ T cells also in an EAE model [3]. It has been suggested that CD8+ T cells remain in the CNS (e.g., brain and spinal cord) as tissue-resident cells, and upon re-encounter of their cognate antigen, focally propagate neuroinflammation [18].
Despite the fact that MS is considered a T lymphocyte-mediated disease [35], the important results of anti-CD20 therapy (e.g., rituximab, ocrelizumab) in MS indicate a significant role for B cells in its pathogenesis. B cells can have either a pro- or an anti-inflammatory role, based on their subtype and context. Their pro-inflammatory functions, comprise critical antigen presentation in the context of MHC class II molecules to Th17 and Th1 cells, secretion of pro-inflammatory cytokines (e.g., tumor necrosis factor alpha, TNF-α, interleukin-6 (IL-6) and granulocyte-macrophage colony-stimulating factor, GM-CSF) that promote CNS inflammation and propagate demyelination and neurodegeneration, and production of antibodies [36]. B lymphocytes can traffic out of the CNS to the cervical lymph nodes where they can undergo affinity maturation and then re-enter the CNS and promote further damage [3].
B cells are considered a unique population of APCs since, in contrast to other APCs which recognize various exogenous and endogenous antigens, B cells are highly selective (i.e., they specifically recognize only the antigens that are bound to their unique surface B cell receptor). Studies with the EAE model have indicated that some autoantigens, like the highly immunogenic myelin oligodendrocyte glycoprotein (MOG), require their presentation by B cells to activate CD4+ T cells. Accordingly, it can be speculated that the antigen(s) which trigger human MS are likewise B cell dependent [36]. Furthermore, active genes in B cells represent a major component of more than 200 variants known to increase the risk for developing MS. Remarkably, the gene that encodes the MHC class II DR β chain, which is known to be critical for APC function, is considered, genome-wide, the strongest MS predisposition signal. Probably, the net effect of this genetic burden is biased biology of B cells towards a pro-inflammatory phenotype, which promotes the presentation of self-antigens to effector T cells or augments the autoimmune responses through the production of cytokines and other immune mediators [36].
Regulatory T cells (CD4 FoxP3+ Tregs, CD4+ Tr1 regulatory cells, CD8 Tregs), regulatory B cells (Breg) cells and natural killer cells (NK cells) can achieve regulation of effector T cells in the peripheral lymphoid tissue or in the CNS. CD4 FoxP3+ Tregs (<4% of circulating CD4 T cells) express the transcription factor Forkhead box protein 3 (FoxP3) along with numerous inhibitory checkpoint molecules on their surface. They are activated by self-antigens and they suppress the activation of other cell types through a mechanism that requires cell contact [37]. CD4+ Tr1 regulatory cells impede cell proliferation mainly via the secretion of IL-10 [38]. Both Tregs are considered important in MS due to the exhibition of unique characteristics. Subsets of CD8+ Tregs that have been indicated to suppress immune responses and disease progression via distinct mechanisms have been identified by a unique expression of molecules like CD122, CD28, CD102 and HLA-G [2,39,40]. In addition, Th2 cells secreting cytokines like IL-4, IL-5, and IL-13, are considered to be able to downregulate the activity of pro-inflammatory cells [27]. B cells can also regulate various B and T cell mediated effector immune functions via secretion of regulatory cytokines IL-10 and IL-35, transforming growth factor beta (TGF-β), or programmed death-ligand 1 (PD-L1). Specifically, IL-10 secreting B-regs inhibit pro-inflammatory T cell responses, partly mediated via IFNγ and IL17 [2,3,36]. Finally, NK cells are known to suppress immune responses via killing activated, possibly pathogenic, CD4+ T cells.
Immune-modulatory networks are triggered in parallel with the deleterious activity of effector T cells, in order to limit CNS inflammation and initiate tissue repair, resulting in partial remyelination. The modulation of immune activation can be associated with clinical remission. However, it should be mentioned that in the absence of treatment, suppression of autoimmunity cannot be fully achieved. Consequently, additional attacks will normally lead to the progressive form of MS [2]. The action of autoreactive T and B cells in MS could be owed to the defective function of regulatory cells. Disease-associated HLA class II variants might skew the selection in the thymus so that the regulatory T cells which are released into the peripheral sites cannot adequately suppress autoreactive effector T cells [3].
3. MS Therapies
3.1. Disease-Modifying Therapies
Current treatments for MS can be categorized into long-term immunosuppressant drugs, which have significant risks for various infections and cancer, and disease-modifying therapies (DMTs) designed to alter the progress of the disease via interference with B and T cells activity, and reduction of BBB disruption. For example, the more recently engineered monoclonal antibodies (mAbs) act via blocking α4 integrin interactions (e.g., natalizumab) or lysing immune cells exhibiting surface markers like CD20 (ocrelizumab, ofatumumab) [41] or CD52 (alemtuzumab). Due to their different mechanisms of action (Figure 3), DMTs’ efficacy and safety profiles [42] vary significantly. Presently, there exist more than 10 FDA (U.S. Food and Drug Administration) approved DMTs for RRMS aiming to reduce relapse level and severity of inflammation in CNS. DMTs can be classified based on the administration route as intravenous, self-injectable and oral formulations (Table 1) [16,23,31,43,44,45,46,47,48,49].
Figure 3.
Suggested mechanism of action of several disease-modifying therapies (DMTs) (with the permission of [47]).
Table 1.
Disease-modifying-therapies for RRMS (based on [16,23,43,45]).
Among the FDA-approved DMTs, ocrelizumab, alemtuzumab and natalizumab seem to have the highest anti-inflammatory effect and to efficiently reduce relapses as proven by MRI scans [2,50]. Another approach for the treatment of MS involves the use of low-dose interleukin 2 (IL-2). This treatment is based on the weak in vivo response of effector T cells to low-dose IL-2 compared with Foxp3+ Treg cells which proliferate due to the expression of the high-affinity IL-2 receptor (CD25). This treatment has been shown to be well tolerated but, since non-specific expansion of the Foxp3+ Treg population cannot be excluded, it may effect susceptibility to infections and malignancies in some patients [51]. Interestingly, it has been shown that the more aggressive and less selective targeting of immune cells leads to more effective disease suppression, though at the cost of enhanced risk of side effects like infections and neoplasms due to decreased normal immune surveillance [27].
Despite the noteworthy advancements in the treatment of MS, the observed rates of progressive disability as well as of early mortality are still bothersome. Accordingly, there exists a need for safer, well tolerated and highly efficient treatments. This need is even higher for therapies capable of stopping or slowing the progression, and improving the disability in progressive MS [14,16,52,53,54]. Till now, only one therapy (ocrelizumab) appeared to be beneficial for the treatment of PPMS [14,16].
3.2. Antigen-Specific Immunotherapies
The Holy Grail for the treatment of MS is to specifically suppress the disease while at the same time allow the immune system to be functionally active against infectious diseases and malignancy. This could be achieved via the development of immunotherapies designed to specifically suppress immune responses to self-antigens [43,51,58,59,60]. Even though the detailed mechanisms of MS induction have not been fully clarified, a dominant hypothesis is that the loss of immune tolerance to myelin proteins like myelin basic protein (MBP), proteolipid protein (PLP) and myelin oligodendrocyte glycoprotein (MOG) leads to the recruitment of myelin-specific CD4+ T cells, resulting in myelin damage [14,61].
Antigen-specific immunotherapies are based on the introduction of self-antigens to APCs in the absence or presence of very low levels of costimulatory molecules (i) acting directly via TCR on effector T cells resulting in immunological anergy and deletion of pathogenic T cell clones (passive tolerance), and (ii) through activation, expansion, and differentiation of antigen-specific regulatory T cells which secrete anti-inflammatory cytokines (active tolerance) [62,63] (Figure 4).
Figure 4.
Bioconjugate-based approaches for the induction of Ag-specific tolerance in autoimmune diseases. The engineered bioconjugates target autoantigens and tolerogenic molecules to DCs (1); to facilitate antigen-processing via endocytic receptors (2); to hinder costimulation (3); to link to apoptotic cells for tolerogenic presentation (4); and to deliver toxin to autoantigen-specific T cells (5). These strategic approaches lead to peripheral tolerance as a consequence of anergy and deletion of cognate T cells, and/or induction of Tregs (with permission of [62]).
More specifically, an immunological synapse is established between APCs and T cells that is based on the formation of a trimolecular complex (signal 1) comprising the HLA class II molecule on the APC, the antigen (e.g., immunodominant epitope of a myelin protein) bound to this molecule and the TCR [64,65]. The establishment of the immunological synapse is the most vital process for the activation of effector T cells. In the absence of costimulatory molecules (signal 2), T cells become unresponsive to the antigen stimulation, a state known as anergy [65,66]. The presence of a costimulatory molecule exhibiting inhibitory properties could result to clonal deletion via apoptosis of the T cells. Autoreactivity of T lymphocytes can be also suppressed by the induction of regulatory T cells resulting in stable and long-term immune tolerance [59,65]. In vivo experiments have revealed that antigen-specific regulatory T cells are more effective than polyclonal Tregs regarding the control of organ-specific autoimmune diseases [67]. Finally, immune tolerance can be achieved via cytokine induced immune deviation, i.e., skewing of effector T cell subsets from Th1 and Th17 (proinflammatory phenotype) towards Th2 and Tr1 (anti-inflammatory phenotype) [59,65].
Antigen-specific therapies can be categorized according to the nature of the tolerogen (e.g., peptides derived from MBP, PLP, or MOG, mixtures of myelin derived peptides; altered peptide ligands; plasmids encoding myelin derived peptides, peptides related to TCR regions, attenuated myelin-specific T cells, tolerogenic DCs, antigen-coupled cells), the administration route (e.g., intravenous, subcutaneous, intraperitoneal, mucosal, epicutaneous, infusion of Ag-coupled cells) [14,43,51,59,65] and the antigen dose [68]. Since, antigen-specific therapies are thought to combine maximal efficiency with minimal side effects, they could be considered especially appealing [14]. On the other hand, they need to overcome major challenges in order to be efficiently used for the treatment of MS.
The first challenge is that the target antigens in MS are not known and remain to be identified [14,27,65]. The disease is largely heterogeneous. It involves multiple autoantigens (contrary for example to neuromyelitis optica that involves reactivity to Aquaporin-4, AQP4) that can vary between patients depending on genetic characteristics, age, environmental and/or triggering factors, and duration of the disease [2,27,69,70]. It has been assumed that myelin targets like MBP, PLP and MOG are relevant, but this is mainly based on EAE models and not on MS patients. Furthermore, therapeutic efficiency in EAE cannot always be translated in MS. Accordingly, the interpretation of the above remains a crucial challenge for the translation of antigen-specific therapies from bench to bedside [27].
Furthermore, it should be noted that the clinical/neuropathological features of MS change noticeably with time [5,70]. Thus, not all patients will necessarily have similar responses to myelin antigen-specific immunotherapies [5]. Additionally, in chronic MS, the pattern of recognized autoantigens progressively increases during the course of the disease, due to a spread of the adaptive immunity to related self-antigens, a phenomenon recognized as epitope spreading [69,70]. Epitope spreading has been defined as the broadening of epitope specificity from the initial immunodominant epitope-specific immune response to other subdominant protein epitopes [71]. Epitope spreading can be categorized as “intra-molecular” related to shifting of immune responses between different epitopes of the same protein (e.g., MBP) and “intermolecular” related to the shifting of immune responses between two proteins (e.g., MBP and PLP) [27,72]. The hierarchy of immunodominant and cryptic epitopes is supposed to be dependent on a combination of peptide processing and presentation by various APCs, and also on the availability of epitope-specific T lymphocytes, taking into account the mechanisms of central and peripheral tolerance [71]. Accordingly, identifying the autoantigens that should be included in the therapeutic formulation can be rather challenging. This problem might be partially overcome via tolerance spreading, i.e., a gradual spread of the tolerance to the administered autoantigens also to other self-antigens which are involved in autoimmunity [70]. Elucidation of the cellular and molecular mechanisms involved in epitope spreading in MS is very important in order to design efficient antigen-specific immunotherapies for MS patients [71]. In this respect, therapeutic strategies targeting a broader array of epitopes may need to be pursued. Furthermore, since immune reactivity broadens with disease duration, antigen-specific immunotherapies should ideally be delivered early in the course of the disease when epitope spreading has not yet occurred, according to an optimized dosage and frequency schedule [14,27,65,73]. An alternative approach could be to achieve bystander suppression (i.e., modulation of the responses to one target antigen leads to modulation of the responses to neighboring target antigens). However, limiting evidence exists for such therapies [27].
Finally, another challenge regarding the translation of antigen-specific immunotherapies from bench to bedside is that the administration of tolerogenic vaccines to MS patients with inapparent infections could be immunogenic and worsen the course of the disease due to its presentation in the immune system in a pro-inflammatory environment. This has been the case in clinical trials with APL [74]. Thus, a crucial test for tolerogenic vaccines could be the in vivo assessment of their delivery in a proinflammatory environment, either after EAE onset, or by co-delivery of adjuvants and/or pro-inflammatory stimuli during EAE immunization [63].
Continuing research efforts towards the development of effective and safe antigen-specific therapies for MS gave rise to the epicutaneous administration of antigens (e.g., dermal patch loaded with myelin derived peptides) for the establishment of skin-induced immune tolerance in MS. The ability of skin DCs to induce myelin-specific tolerance has already been demonstrated in both in vivo experiments (Table 2) and early clinical trials [28,58]. Finally, oral tolerance has appeared to be efficient regarding the prevention of EAE, but significantly less efficient concerning the therapy of ongoing EAE and MS [75].
4. In Vivo Assessment of Tolerance-Inducing Vaccination in MS
4.1. Animal Model of MS
The typically used animal model of MS is that of the experimental autoimmune encephalomyelitis (EAE) [3,4,18,76,77,78,79,80]. EAE is an acute or chronic neuro-inflammatory brain and spinal cord disease [18] which can be induced in various animal strains such as mice, rats, guinea pigs, rabbits, and even primates [7], via immunization with spinal cord homogenate or with various myelin proteins (e.g., MBP, PLP, MOG) emulsified in complete Freund’s adjuvant (active EAE) [7,78,81]. EAE can be also transferred to naïve mice via adoptive transfer of T cells specific for myelin [8,78]. In EAE, myelin peptides are presented on MHC class II molecules to autoreactive T cells, together with costimulatory molecules (e.g., CD80 and CD86), resulting in activation of the T lymphocytes and, consequently, in an autoimmune attack on the myelin sheath [79]. EAE is principally mediated by myelin specific CD4+ T cells [20,78,82,83]. The clinical course of EAE varies based on the immunized animal species and the encephalitogenic antigen used for the inoculation. Usually the animals experience either an acute monophasic, progressive or not, disease, or a chronic relapsing-remitting disease. Ataxia, weight loss, sagging hind limb and paralysis are among the typical clinical signs of EAE [78]. Interestingly, various effective RRMS therapies (e.g., anti-inflammatory, immunomodulatory therapies) have been developed with the aid of EAE models. However, to date, no EAE model exists, that is capable of reproducing the specific features (e.g., clinical and neuropathological) of progressive MS. Therefore, despite the undeniable value of EAE for basic research concerning the mechanisms of brain inflammation and immune mediated CNS tissue damage, its value as model for MS is limited [18].
4.2. Myelin Peptide-Based Vaccination
4.2.1. Immunodominant Myelin Petides
Myelin is a multilaminar sheath around nerve fibers comprising lipid bilayers and different proteins. The major myelin proteins are MBP and PLP which represent more than 75% of the total myelin protein. Additionally, myelin contains MOG [84] representing ~0.05% of the myelin proteins [7], myelin-associated oligodendrocyte basic protein (MOBP), oligodendrocyte-specific protein (OSP), myelin-associated glycoprotein (MAG), and Nogo-A [85].
While the etiology of MS is not clear yet, a favored hypothesis supported by experimental evidence indicates that the cross-reactive immune response between myelin derived epitopic peptides and viral or bacterial components can be considered as an important factor that contributes to the development of autoimmune T cells which initiate a demyelinating inflammatory response. Thus, the determination of the main epitopes of the encephalitogenic myelin and/or neuronal proteins that are implicated in MS is considered of major significance both for the development of antigen-specific therapies for MS and the elucidation of MS pathophysiology and etiology [85].
In recent decades, extensive studies have been performed aiming to identify the immunodominant epitopes recognized by T lymphocytes in MS. These studies have revealed that only the myelin proteins MBP, PLP, MOG, MOBP, and OSP can induce clinical EAE in laboratory animals and that autoimmune T cells against these proteins can be detected in MS patients. Other myelin proteins, like MAG and Nogo-A have been also identified as encephalitogenic proteins. Finally, some neuronal components (e.g., β-Synuclein, Neurofilament) have been found to exhibit encephalitogenic potential [85]. Antigen recognition takes place in the setting of a trimolecular complex formed by HLA, myelin peptide and TCR [64,86,87]. The immunodominant PLP epitopes which can be processed by human APCs lie within the PLP regions 30–60 and 180–230. Similarly, the PLP epitopes that activate T lymphocytes in EAE are within the 40–70, 90–120 and 180–230 regions of the protein [5]. Immunodominant epitopes of MOG that are recognized by encephalitogenic T cells in MS as foreign antigens are MOG1–22, MOG35–55 and MOG92-106 with the 35–55 epitope being the major immunodominant region of MOG [86]. Analysis of T-cell responses to MOBP in SJL/J mice indicated MOBP15-36 as the main encephalitogenic epitope of MOBP [85].
A cyclic analogue of MBP87–99 has been designed by Matsoukas and coworkers taking into consideration HLA (His88, Phe90, Ile93) and T-cell (Phe89, Lys91, Pro96) contact side-chain information. cyclo(87-99)MBP87–99 was shown to induce EAE, bind HLA-DR4, and enhance CD4+ T-cell proliferation, similarly to the linear MBP87–99 peptide [83]. Additionally, peptide analogues derived from the encephalitogenic peptide MBP82–98, the altered peptide ligand MBP82–98 (Ala91) and their cyclic analogues were synthesized by Deraos and coworkers and assessed regarding their binding to HLA-DR2 and HLA-DR4 alleles involved in the presentation of myelin epitopes to T cells. The cyclic MBP82–98 was shown to bind strongly to HLA-DR2 and to have a lower affinity to the HLA-DR4 allele. Both the cyclic and APL analogues of MBP82–98 were found to be promising and were selected to be further evaluated regarding their ability to modulate the responses of autoreactive T cells in MS [88]. In addition to the abovementioned studies, Tapeinou and coworkers developed a peptide compound comprising the MBP85–99 immunodominant epitope coupled to an anthraquinone derivative (AQ) via a disulfide (S-S) and six amino hexanoic acid (Ahx) residues. AQ-S-S-(Ahx)6MBP85–99 was found to bind reasonably to HLA II DRB1*-1501 antigen indicating the possibility of eliminating encephalitogenic T lymphocytes through generation of a toxic, thiol-containing moiety (AQ-SH) [89].
Yannakakis and coworkers used molecular dynamic simulations to study the interactions of the MOG epitope MOG35–55 with the HLA and TCR receptors during the formation of the trimolecular complex TCR-hMOG35–55-HLA DR2 [64]. They also used robust computational methods (e.g., molecular dynamics, pharmacophore modeling, molecular docking) to rationally design non-peptide mimetic molecules capable of binding with enhanced affinity to the T-cell receptor and not to the MHC-peptide complex, thus impeding the formation of the trimolecular complex [90].
To date various studies have assessed different myelin epitopes, as single peptides or mixtures of them, regarding their ability to induce antigen-specific tolerance in EAE animal models (Table 2).
Table 2.
Myelin protein/peptide-based vaccination.
4.2.2. Altered Peptide Ligands (APLs)
Altered peptide analogues (APLs) of the immunodominant myelin protein epitopes have been successfully synthesized and applied in antigen-specific immunotherapies in vivo (Table 2). They are molecules where one or more amino acids in the sequence of the native immunodominant peptides, crucial for the interaction with the TCR, have been substituted. Depending on the substitutions, APLs can induce protective or therapeutic immune responses against EAE [91]. APLs can change agonist peptides into antagonist ones. Antagonistic peptides participating in the trimolecular complex MHC-peptide-TCR and causing suppression of EAE exhibit loss of their side chain interactions with the complementarity determining region 3 (CDR3) loop of the TCR. Substitution of large side chains interacting with the TCR with small side chain amino acids (e.g., Ala) causes antagonism and, therefore, inhibition of EAE symptoms. Moreover, APLs can switch Th1 cell response towards Th2 thus leading to disease suppression. Finally, APLs might activate regulatory T cells capable of antagonizing the deleterious actions of encephalitogenic cells in the CNS [83,87]. Accordingly, mutant cyclic peptides of MBP87-99 (e.g., cyclo(91-99)[Ala96]MBP87-99 and cyclo(87-99)[Arg91Ala96]MBP87-99) were shown to suppress the proliferation of a CD4 T-cell line from a MS patient, bind to HLA-DR4 and exhibit an increased Th2/Th1 cytokine ratio in peripheral BMCs derived from MS patients [83].
Molecular dynamics were applied by Mantzourani and coworkers to study the interactions of the MBP87–99 epitope and its antagonistic APLs (e.g., [Arg91, Ala96] MBP87-99 and [Ala91,96] MBP87–99) with the receptor HLA-DR2b [92].
4.2.3. Y-MSPc
Kaushansky and coworkers [93,94] pursued a “multi-epitope-targeting” approach aiming to simultaneously neutralize T lymphocytes reactive against various major encephalitogenic epitopes. In this respect, they designed a recombinant synthetic protein comprising multiple epitopes of the human myelin protein (Y-MSPc). Y-MSPc was shown to efficiently inhibit the development of EAE induced in mice by a single epitope of myelin protein (classical EAE) or by a cocktail of five different encephalitogenic peptides (complex EAE) and suppress its progression, outperforming the single disease-specific epitope and the.mixture of peptides (Table 2).
4.2.4. Cytokine-Neuroantigen (NAg) Fusion Proteins
Fusion proteins consisting of a cytokine (N-terminal domain) fused with or without an appropriate linker to a neuroantigen (C-terminal domain) represent an emerging platform for antigen-specific vaccination [95,96]. Regarding their mechanism of action, the cytokine domain of the vaccine exhibits high affinity binding to specific surface cytokine receptors on certain subsets of APCs. This results in highly efficient uptake of the neuroantigen domain by these APCs, and its processing and presentation on MHC class II molecules to NAg-specific T lymphocytes. NAg tolerogenic presentation is assumed to induce regulatory responses and results in the establishment of antigen-specific immunological tolerance (Figure 5) [96,97].
Figure 5.
Mechanism of action of cytokine-NAg fusion proteins [96].
Various single-chain cytokine-neuroantigen (NAg) fusion proteins (e.g., granulocyte-macrophage colony-stimulating factor (GMCSF)-NAg, IFNβ-NAg, IL16-NAg, IL2-NAg), where NAg comprises self-myelin epitopes, have been examined as potential tolerogenic and/or therapeutic antigen-specific vaccines in EAE mouse models (Table 2). The developed fusion proteins have been found to target APCs and to effectively prevent the induction of EAE when administered prophylactically as well as to suppress pre-developed EAE. Due to their combined preventive and therapeutic activities, the cytokine-NAg vaccines were characterized as both tolerogenic and therapeutic.The ranking order with respect to their inhibitory activity was the following: GMCSF-NAg, IFNβ -NAg > NAgIL16 > IL2-NAg > MCSF-NAg, IL4-NAg, IL-13-NAg, IL1RA-NAg. [96].
Apart from the aforementioned cytokine-NAg fusion proteins, the macrophage colony stimulating factor (MCSF)-NAg fusion protein was used in order to increase the presentation of NAg by macrophages. However, it was found to be less tolerogenic than GMCSF-Nag, thus indicating the latter fusion protein as the most suitable for antigen-specific vaccination [95,98]. Additionally, it was revealed that GMCSF-MOG does not require a non-inflammatory quiescent environment to effectively prevent the development of EAE which contradicts the previous knowledge regarding tolerogenic vaccines [95,98].
4.2.5. Antibodies Coupled with Myelin Peptides
The dendritic and epithelial cell receptor with molecular weight equal to 205 kDa (DEC205) is expressed by DCs and enables antigen presentation. Injection of antigens (Ags) coupled to antibodies (Abs) specific for DEC205 into mice, at a low dose (e.g., ≤ 0.1 μg of fusion mAb [99]) leads to Ag presentation by nonactivated DCs, resulting in induction of regulatory T lymphocytes. In this respect, fusion of αDEC-205 Abs with MOG35–55 [100] and PLP139–151 [101] ameliorated EAE in mice. Similarly, Ring and coworkers synthesized single chain fragment variables (scFv) specific for DEC205. scFvs were subsequently fused with MOG (scFvDEC:MOG) and administered to mice both before and after induction of EAE. Significant prevention of EAE was observed by vaccination with scFv DEC:MOG before immunization. In addition, administration of scFv DEC:MOG post immunization led to substantial alleviation of the clinical symptoms of the disease [102]. On the other hand, Tabansky and coworkers targeted the dendritic cell inhibitory receptor 2 (DCIR2) receptor with αDCIR2 Abs fused to PLP139–151 and observed significant alleviation of EAE clinical symptoms [79]. In another approach, Kasagy and co-workers demonstrated that administration of anti-CD4 and anti-CD8 Abs followed by injection of PLP139–151 resulted in substantially lower EAE scores and reduced rate of relapses in chronic disease in mice [103] (Table 2).
4.2.6. Recombinant T-cell Receptor Ligands (RTLs)
Antigen-specific immunosuppression can be induced via the utilization of MHC-peptide complexes as specific TCR ligands interacting with autoimmune T cells in the absence of co-stimulatory molecules. A recombinant TCR ligand (RTL) typically comprises a single polypeptide chain encoding the β1 and α1 domains of MHC class II molecules linked to a self-antigen [104] and represents the minimal interactive surface with antigen-specific TCR. RTLs fold in a similar manner to native four-domain MHC/peptide complexes but they deliver qualitatively different, suboptimal signals which cause a “cytokine change” to anti-inflammatory factors in targeted autoreactive T cells. Treatment with RTLs could reverse the clinical/histological signs of EAE in different experimental cases (e.g., MBP-induced monophasic disease, MOG peptide-induced chronic EAE, PLP-induced relapsing remitting EAE) and even promote recovery of myelin and axons in mice with chronic disease [105,106,107] (Table 2).
Alternatively, RTLs could involve natural or recombinant α1α2 and β1β2 MHC class II domains covalently or noncovalently linked with encephalitogenic or other pathogenic peptides. These specific RTLs could bind both to the TCR and the CD4 molecule on the T cells surface via the β2 MHC domain and were shown to hinder the activation of T cell and thus prevent EAE in rodents [108].
4.2.7. Bifunctional Peptide Inhibitors (BPIs)
Bifunctional peptide inhibitors (BPIs) are a promising novel class of peptide conjugates which are designed to selectively impede the maturation of myelin specific T cells. They comprise an immunodominant myelin protein epitope tethered to a signal-2-blocking peptide derived from lymphocyte function-associated antigen-1, LFA-1 (i.e., a T cell protein binding to intercellular adhesion molecule-1, ICAM-1) [109] (Figure 6). It is hypothesized that they bind at the same time to MHC-II and ICAM-1 on APCs thus inhibiting the immunological synapse formation during APC and T cell interactions [110]. The development of molecules that could target more than one epitope is crucial for the application of BPI technology in MS [111]. The performance of BPIs with respect to the induction antigen-specific immune tolerance has been studied in EAE animal models (Table 2).
Figure 6.
Sortase-mediated addition of two different antigens (A) PLP and (B) MOG to the C-terminus of LABL-Fc-ST (with permission of [109]).
4.2.8. Antigen-Drug Conjugates
Antigen drug conjugates (AgDCs) combine two therapeutic approaches (e.g., antigen-specific immunotherapies and immunomodulatory agents) to treat autoimmune diseases. Via chemical conjugation, the Ag could target the immunomodulatory agent to diseased cells thus minimizing side effects. AgDCs are assumed to exhibit increased affinity specificity through targeting cognate B cell receptors or endogenous autoantibodies. AgDCs formation entails the selection of an appropriate pair of antigen and immune modulator, and a linking scheme. An AgDC combing PLP139–151 and dexamethasone (PLP139−151-DEX) was administered to mice induced with EAE. It was shown that the AgDC protected the mice from developing clinical symptoms during the 25-day study [61] (Table 2).
4.3. DNA Vaccination
Deoxyribonucleic acid (DNA) vaccination is considered a promising antigen-specific approach for the treatment of MS [91,136,137,138]. DNA plasmid vaccines for tolerance induction in MS comprise a bacterial plasmid encoding myelin antigen(s). Expression is controlled by a mammalian promoter and a transcription terminator. They are administered either as naked DNA or with the aid of carriers (e.g., cationic lipids, cationic liposomes, polymeric particles), via the intramuscular or intradermal (e.g., “gene gun” delivering gold particles coated with pDNA vaccines) administration routes. Vaccination leads to DNA uptake and gene expression by the cells at the injection site [139,140]. Induction of immune tolerance is achieved via the following potential mechanisms (Figure 7). After intramuscular injection, myocytes are the main transfected cells, as well as few APCs. Antigens are then presented by the following mechanisms: i) myocytes process and present the antigen to T cells leading to T cell anergy ii) myocytes produce and secrete antigen that is taken up by APCs, which subsequently activate T cells. This results in loss of T cell co-stimulation through CD28, downregulation of IL-2, production of IFN-γ and reduced T cell proliferation. Intramuscular injection can also induce IFN-β via TLR9 activation due to the presence of CpG in the plasmid backbone [140], leading to downregulation of IL-12, IFN-γ, and Th17 cell responses. Following intradermal administration, DNA is delivered directly into the resident APCs (e.g., Langerhans and dermal cells). Intradermal vaccination leads to the secretion of regulatory cytokines (e.g., IL-4, IL-10, and TGF-β) thus resulting in the induction of anti-inflammatory Th2 immune responses [139,141]. Balance between tolerance induction and inflammatory immune response can be controlled by the administration route, antigen dose, and modification of the DNA-encoded antigen [141]. Numerous data from in vivo studies with the EAE animal model (Table 3), have demonstrated the efficiency of DNA plasmid vaccines at inhibiting MS via inducing T regulatory cells or anergy, clonal deletion, and immune deviation [139].
Figure 7.
Mechanisms of immune tolerance induction by DNA plasmid vaccines (with permission of [139]).
Table 3.
DNA vaccination.
4.4. Cell-Based Vaccination
4.4.1. Antigen-Specific Tolerogenic Dendritic Cells (tolDCs)
Dendritic cells (DCs) have a critical role in initiating adaptive immune responses in order to eliminate invading pathogens as well as in inducing tolerance towards innocuous components so as to maintain immune homeostasis [149]. Tolerogenic dendritic cells (TolDCs) are considered an attractive therapeutic approach for the induction of antigen-specific tolerance in autoimmune diseases [150,151]. To date various protocols have been developed for the in vitro generation of clinical-grade tolerogenic DCs ([35, 152] (Figure 8) [153]) for antigen-specific immunotherapies. Autologous peripheral blood mononuclear cells (PBMCs) or bone marrow derived cells (BMDCs) are differentiated into tolDCs by numerous pharmacologic agents (e.g., immunosuppressive drugs such as rapamycin, cytotoxic T-lymphocyte-associated protein 4 (CTLA-4) Ig, corticosteroids; cyclic AMP inducers such as prostaglandin E2 and histamine; chemicals like vitamin D3, aspirin, etc.; proteins and neuropeptides like HLA-G, vasoactive intestinal peptide, etc.) and immunomodulatory cytokines (e.g., IL-10, TGF and low doses of GM-CSF) [150,153] and are further pulsed in vitro with autoantigens, encephalitogenic peptides, apoptotic cells, etc. [153]. tolDCs can display an immature or a semi-mature phenotype which is characterized by altered cytokine production and low expression of MHC and co-stimulatory molecules [150].
Figure 8.
Strategies to generate tolDCs for clinical therapeutics [153].
Depending on the experimental protocol, the molecules used to induce tolerogenic properties, and the targeted cell population, tolDCs use different mechanisms of regulation to induce tolerance (Figure 8), including conversion to a regulatory T cell phenotype, induction of anergy, and antigen-specific deletion of T cell clones [19,35,150,152,153,154]. Lately, their ability to induce regulatory B cells secreting IL-10 has been also demonstrated [152]. TolDCs can be categorized into induced tolDCs (itDCs) (i.e., those acquiring their tolerogenic features in vitro or in vivo as described above and contribute to the maintenance of tolerance even under proinflammatory conditions) and natural tolDCs (ntDCs) (i.e., DCs present in the spleen and other lymphoid sites which inherently aid to establish tolerance in the absence of danger signals) [155].
The therapeutic potential of tolDCs has been demonstrated in the EAE model of MS (Table 4) (Figure 9). A key challenge is the translation of the in vivo results to humans. In this respect, it will be critical to correlate clinical efficiency with variation of immunological parameters and, accordingly, to define the best administration route and the effective dose of cells for this route [152]. Progress in the scientific areas of recombinant protein expression, genome editing and nanotechnology-based drug delivery systems, combined with improved immunization protocols, could further improve the promising tolDC vaccination in the furure [150].
Table 4.
Cell-based vaccination.
Figure 9.
Evaluation of inflammatory lesion load within the spinal cord of tolDC-treated and PBS-treated mice using ex vivo MRI imaging. (A) Representative MRI of spinal cord with hyperintense white matter spots marked with a red arrow. Two representative axial slices are shown per treatment group. (B) The total number of hyperintense white matter spots along the entire spinal cord was quantified as a measure of lesion load in three mice per treatment group. Results are presented as individual scores for hyperintense spots with median [154].
4.4.2. T Cell Vaccination (TCV)
T cell vaccination involves the extraction of myelin reactive T cells from MS patients and their re-injection after irradiation in order to induce protective immunity [12,80,141,156]. To prepare T-cell vaccines, CSF mononuclear cells or blood PBMC’s are stimulated with myelin antigen, and are then expanded specifically for the selected myelin peptide till an adequate population of cloned T cells is available. The latter are activated with antigen, and attenuated via exposure to radiation (6–12,000 Rads) to avoid proliferation after injection [156,157]. In clinic, the TCV protocol also involves multi-epitope TCR peptides [80]. TCV has been found to specifically suppress autoreactive T cells in MS via induction of a complicated anti-ergotypic and anti-idiotypic regulatory network or T cell deletion [80,91,156]. Various typical cytokines and lymphocyte phenotype transfer have been shown to participate in the depletion of the autoreactive T cells and the reversion of abnormal autoimmune responses [80] (Figure 10).
Figure 10.
Complexity of anti-vaccine responses induced by TCV (with permission of [29]).
4.4.3. Antigen-Coupled Cells
Intact proteins (e.g., myelin proteins) as well as multiple peptides (e.g., MBP, PLP, and MOG derived peptides) can be coupled to a single cell (e.g., splenocyte [158,159], erythrocyte [67,160]) [86] (Table 4), thus permitting concurrent targeting of various T-cell specificities. This could be critical for antigen-specific immunotherapy in MS, where immune tolerance to multiple T-cell epitopes is considered necessary for the disease treatment due to epitope spreading. Contrary to protein/peptide-induced tolerance, vaccination with protein/peptide-coupled cells lowers the risk of anaphylaxis, since the antigen is chemically crosslinked to the cell surface. Vaccination with antigen-coupled cells has been found to prevent the active- and passive-transfer. Finally, tolerance induction with Ag-coupled cells can help define immunodominant myelin antigens, since the disease progression can be impeded by cells coupled with the spread epitope [75].
4.5. Carrier-Aided Vaccination
In recent decades, different strategies have been pursued for the development of carriers [175,176,177,178,179] loaded/conjugated with myelin antigens or combinations of myelin peptides and immunomodulating agents. The developed carriers have been designed to target TCR signaling pathways, as well as cytokines and co-signaling molecules, aiming to enhance TCR-mediated tolerance [30,62,177]. Various biomaterials (e.g., polymers, lipids) have been formulated into micro- or nanoparticles, self-assembled into different structures, or formed molecular conjugates with self-antigens (e.g., conjugation of self-antigens with polymers, antibodies, small molecules). Both nanoparticles (NPs) and microparticles (MPs) can be uptaken by APCs thus enhancing the intracellular delivery of myelin antigens and imunnomodulators [180,181].
4.5.1. Polymer Particles
Polymer micro- and nanoparticles loaded with self-antigens and/or immunomodulatory molecules have recently emerged as ideal carriers for tolerogenic vaccines since their properties (e.g., particle size, composition, antigen/immunomodulator loading) can be fine-tuned to induce peripheral tolerance. Furthermore, NPs can be employed as platforms to regulate the doses and delivery times not only of the self-antigens but also of the tolerogenic adjuvants that are required to promote tolerance [70].
Poly(lactic-co-glycolic acid) (PLGA) NPs are non-toxic, biodegradable/biocompatible and have the advantage of being FDA approved for various clinical uses including drug delivery, diagnostics, etc. Additionally, surface functionalization strategies may improve their interaction with cells, thus optimizing cell targeting and vaccine performance. PLGA NPs are the most extensively assessed nanocarriers in pre-clinical models of autoimmune diseases and their effectiveness regarding antigen-specific immunotherapies (Table 5) represents a proof-of-concept of the feasibility of nanoparticle-aided tolerogenic vaccination. Furthermore, their successful application in animal models appears encouraging concerning potential translation to humans [70].
Table 5.
Carrier-aided vaccination.
4.5.2. Soluble Antigen Arrays
Soluble antigen arrays (SAgAs) are synthesized by co-grafting the immunodominant epitope PLP139–151 and LABL peptide (i.e., ligand of the intercellular adhesion molecule 1, ICAM-1) to hyaluronic acid (HA) via a hydrolysable oxime bond [182,183]. Their size can be fine-tuned to allow them to drain to the lymph nodes [183]. Another key factor affecting their drainage is the injection site and the molecular weight of HA. For example, following s.c. injection, HA can drain to the lymphatics and its retention time can be affected by its molecular weight [183].
The efficiency of the hydrolysable SAgAPLP-LABL to suppress disease in mice with EAE has been reported in various studies (Table 5) and has been attributed to the simultaneous delivery of the myelin derived antigen and the cell adhesion signal [182]. Furthermore, earlier in vitro studies indicated that SAgAs demonstrate Ag-specific binding with B lymphocytes, target the B cell receptor (BCR) and reduce BCR-mediated signaling [184]. Based on the abovementioned experimental results indicating BCR engagement as the mechanism of action of SAgAPLP-LABL Hartwell and coworkers developed a novel version of SAgAPLP-LABL, the cSAgAPLP:LABL (click SAgA), employing non-hydrolysable conjugation chemistry (e.g., copper-catalyzed azide-alkyne aycloaddition) [184,185]. cSAgAPLP:LABL was found to significantly reduce or inhibit BCR-mediated signaling and to exhibit enhanced in vivo efficiency in comparison with the hydrolytically unstable SAgAPLP-LABL [184,185] (Figure 11).
Figure 11.
EAE in vivo response to click conjugates (cHA, cHALabl, cHAPLP, and cSAgAPLP:LABL) as measured by (A) clinical disease score and (B) percent weight loss. EAE in vivo response to groups containing both PLP and LABL (cHA+PLP+LABL, SAgAPLP:LABL, cHAPLP+cHALABL, and cSAgAPLP:LABL) as measured by (C) clinical disease score and (D) percent weight loss. Data represent mean ± SD (n = 5); statistical significance compared to PBS negative control was determined by two-way ANOVA. (E) Cumulative EAE in vivo response as measured by clinical disease score area under the curve (AUC) derived from subfigures A and C. Data represent mean ± SEM (n = 5); statistical significance compared to PBS negative control was determined by ordinary one-way ANOVA followed by Dunnett’s post hoc test. (* p < 0.05, ** p < 0.01, # p < 0.001, ## p < 0.0001, color coded according to group) (with permission of [185]).
4.5.3. Immune Polyelectrolyte Multilayers (iPEMs)
It has been recently shown that excess signaling via inflammatory pathways such as toll-like receptors (TLRs) is involved in the pathogenesis of autoimmune diseases. Accordingly, the co-delivery of immunodominant myelin peptides with GpG oligonucleotide, a regulatory ligand of TLR9, could potentially limit TLR signaling during the differentiation of myelin-specific T lymphocytes, thus redirecting their differentiation towards a tolerogenic phenotype like the regulatory T cells. In this respect, immune polyelectrolyte multilayers (iPEMs) were formed using a layer-by-layer approach to co-assemble modified myelin peptides with GpG oligonucleotide. These nanostructures have key characteristics of biomaterial-based nanocarriers, such as tunable physicochemical properties and loading capacity, ability to deliver various active ingredients, etc., lacking, however, synthetic components that could exhibit inflammatory properties.
In in vitro studies, iPEMs have been shown to limit TLR9 signaling, decrease activation of DCs, and polarize myelin-specific T lymphocytes towards a tolerogenic phenotype. Additionally, they have been found to reduce inflammation and induce tolerance in mice with EAE [186,187] (Table 5).
4.5.4. pMHC-Nanoparticles (pMHC-NPs)
The “two signal theory” states that two different signals are required for the activation of naive T cells: (i) engagement of the TCR with its cognate pMHC target, and (ii) a co-stimulatory signal from molecules selectively expressed on professional APCs’ surface. It is well known that engagement of the TCR on the surface of a naive T cell without co-stimulation results in the induction of apoptosis or anergy.
The development of pMHC-nanoparticles (pMHC-NPs) for the treatment of autoimmune diseases was based on the hypothesis that pMHC-coated NPs would diminish the responses of autoreactive T cells more efficiently compared with soluble pMHC complexes. This could be due to (i) their multimeric valency, (ii) their potentially superior TCR cross-linking properties compared with “artificial APCs”, and (iii) the protection of the NP-bound pMHC molecules from degradation [104]. The ability of pMHC-NPs to stop the progression of EAE was assessed with in vivo experiments in mice (Table 5).
4.5.5. Mannan-Peptide Conjugates
Based on previous studies with the yeast polysaccharide, mannan, Tseveleki and coworkers, examined mannan conjugation with immunodominant myelin epitopes as an approach to divert the differentiation of myelin-specific T lymphocytes towards a regulatory phenotype, thus decreasing the mice susceptibility to EAE. It was shown that the administration of the synthesized conjugates to mice in both prophylactic and therapeutic vaccination protocols resulted in the induction of antigen-specific T cell tolerance and significant amelioration of EAE clinical and histopathological symptoms. [188] (Figure 12) (Table 5). According to these results, it was speculated that conjugation of MOG epitopes to mannan may modulate the autoimmune response in humans, thus potentially reducing the symptoms of MS [188].
Figure 12.
(a) Mean clinical scores of MOG-EAE in groups of mice vaccinated i.d. with OM-MOG, RM-MOG, OM, RM, or PBS at indicated time points (arrows) before immunization for EAE induction. (b) Mean clinical scores of MOG-EAE in groups of mice vaccinated i.d. at indicated time points (arrows) relative to immunization. (c) Mean clinical scores of MOG-EAE in groups of mice injected i.d. at indicated time points (arrows) after immunization. The results shown are from one representative of two (b,c) or three (a) independent experiments. (d,e) Vaccination with OM-MOG protects C57BL/6 mice from spinal cord inflammation and demyelination during MOG-EAE. (d) Inflammatory cell infiltration (left column) and demyelination (right column) were visualized on day 24 following immunization. (e) Quantification of spinal cord inflammation (black bars) and demyelination (grey bars) as well as brain demyelination (white bars) in all experimental groups. Representative data from five animals per group are shown. Statistical significance after comparisons between groups of mice (using the Kruskal-Wallis test) or histopathology indices (using Student’s t test) is shown (*, p < 0.05). Triangles (a) indicate time points where pair-wise comparison between OM-MOG and RM-MOG groups also show significant differences (with permission of [188]).
4.5.6. Liposomes
Liposomes are tiny vesicles featuring an aqueous core surrounded by a lipid bilayer. They can encapsulate both hydrophilic and hydrophobic drugs and target them to specific cell surfaces via appropriate functionalization. Various types of liposomes have been already approved for clinical use (e.g., delivery of therapeutics, vaccination) and can be designed to induce or tolerate immune responses [189]. Pujol-Autonell and coworkers reported the beneficial effect of MOG peptide loaded liposomes in treating mice with EAE. Liposomes successfully delayed the onset, suppressed the severity and decreased the incidence of the disease [190]. Similarly, Belogurov and co-workers demonstrated that mannosylated liposomes containing MBP46–62 could significantly reduce EAE clinical signs in Dark Agouti (DA) rats [189]. Interestingly liposomes loaded with MBP46–62, MBP124–139, and MBP147–170 and targeting CD206 were proven to be safe and well-tolerated and to normalize cytokine levels in RRMS and SPMS patients [191,192].
4.5.7. Microneedle Patches
Pires and coworkers proposed the use of minimally invasive microneedle patches for the delivery of myelin peptides, as an alternative therapeutic strategy for skin mediated antigen-specific immune tolerance in MS [178].
5. Clinical Trials
Various tolerance-inducing vaccination approaches (e.g., immunodominant myelin epitopes, APLs, DNA vaccination, attenuated autologous myelin reactive T cells, tolerogenic DCs, TCR peptide vaccination, nanocarriers loaded with encephalitogenic myelin peptides, etc.) with promising outcomes in experimental MS models have already reached the clinical development phase. Their safety, feasibility, and efficiency in inducing antigen-specific immune tolerance and reducing MRI-detected disease activity in patients with relapsing remitting and progressive MS have been preliminary demonstrated in phase I and II clinical trials [14,136,139] (Table 6).
Table 6.
Clinical trials.
6. Conclusions
Several exciting vaccination strategies targeting the induction of antigen-specific immune tolerance in MS have been developed during the last decades, based on a single epitope or cocktails of immunodominant epitopes of myelin proteins, altered peptide ligands, DNA vaccines, tolerogenic DCs pulsed with myelin peptides, attenuated autologous myelin reactive T cells, TCR peptide vaccines, conjugates of autoantigens with various types of cells, and different types of carriers (e.g., particles, vesicles, self-assembled structures, or molecular carriers) associated with myelin epitopes. Most of these approaches have demonstrated promising results in animal models of experimental autoimmune encephalomyelitis both in prophylactic and therapeutic vaccination protocols. They successfully prevented the disease or delayed the disease onset, reduced its clinical and pathological symptoms and decreased the number of relapses, or, in a therapeutic scheme, they reversed the clinical and histological signs of the disease. Accordingly, numerous of the abovementioned strategies reached the clinical development phase, and their safety, feasibility, and efficacy were assessed in both phase I and II clinical trials. However, the results from these trials have not indicated the same level of efficiency as in preclinical models. Even though different tolerance-inducing vaccination strategies were proven safe and well tolerated, and in some cases succeeded in inducing tolerogenic responses to patients, no major advances have been reported with respect to clinical efficiency. Consequently, despite the intensive research efforts, up to the present time, no FDA approved antigen-specific immunotherapy is available for treating MS patients. It appears that antigen-specific immunotherapies still face various major challenges such as the involvement of multiple autoantigens that can vary between patients, the epitope spreading, the vaccination of patients with inapparent infections, etc. These challenges need to be overcome in order to allow tolerogenic vaccines to play a major role in the treatment of MS patients. Progress in the scientific areas of recombinant protein expression, genome editing, and smartly designed carriers, combined with better understanding of MS immunopathogenesis and improved immunization protocols, could potentially improve these vaccination strategies in the future. Additionally, further clinical studies, such as phase II and III, including placebo groups, will be required in order to more realistically assess the clinical effectiveness of these interesting antigen-specific immunotherapies in both RRMS and SPMS patients.
Author Contributions
O.K. and C.K. contributed equally to the conceptualization, writing/preparation of the original draft, and writing—review and editing of the final paper. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Harrington, E.P.; Bergles, D.E.; Calabresi, P.A. Immune cell modulation of oligodendrocyte lineage cells. Neurosci. Lett. 2020, 715, 134601. [Google Scholar] [CrossRef] [Scilit]
- Baecher-Allan, C.; Kaskow, B.J.; Weiner, H.L. Multiple sclerosis: Mechanisms and immunotherapy. Neuron 2018, 97, 742–768. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dendrou, C.A.; Fugger, L.; Friese, M.A. Immunopathology of multiple sclerosis. Nature Rev. Immunol. 2015, 15, 545–558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Afshar, B.; Khalifehzadeh-Esfahani, Z.; Seyfizadeh, N.; Danbaran, G.R.; Hemmatzadeh, M.; Mohammadi, H. The role of immune regulatory molecules in multiple sclerosis. J. Neuroimmunol. 2019, 337, 577061. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Greer, J.M.; Pender, M.P. Myelin proteolipid protein: An effective autoantigen and target of autoimmunity in multiple sclerosis. J. Autoimmun. 2008, 31, 281–287. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iwanowski, P.; Losy, J. Immunological differences between classical phenothypes of multiple sclerosis. J. Neurol. Sci. 2015, 349, 10–14. [Google Scholar] [CrossRef] [Scilit]
- Lee, D.-H.; Linker, R.A. The role of myelin oligodendrocyte glycoprotein in autoimmune demyelination: A target for multiple sclerosis therapy? Expert Opin. Ther. Targets 2012, 16, 451–462. [Google Scholar] [CrossRef] [Scilit]
- Rangachari, M.; Kuchroo, V.K. Using EAE to better understand principles of immune function and autoimmune pathology. J. Autoimmun. 2013, 45, 31–39. [Google Scholar] [CrossRef] [Scilit]
- Lüssi, F.; Zipp, F.; Witsch, E. Dendritic cells as therapeutic targets in neuroinflammation. Cell. Mol. Life Sci. 2016, 73, 2425–2450. [Google Scholar] [CrossRef] [Scilit]
- Ho, P.P.; Fontoura, P.; Platten, M.; Sobel, R.A.; DeVoss, J.J.; Lee, L.Y.; Kidd, B.A.; Tomooka, B.H.; Capers, J.; Agrawal, A.; et al. A Suppressive oligodeoxynucleotide enhances the efficacy of myelin cocktail/IL-4-tolerizing DNA vaccination and treats autoimmune disease. J. Immunol. 2005, 175, 6226–6234. [Google Scholar] [CrossRef] [Scilit]
- Hemmer, B.; Nessler, S.; Zhou, D.; Kieseier, B.; Hartung, H.-P. Immunopathogenesis and immunotherapy of multiple sclerosis. Nat. Clin. Prac. Neurol. 2006, 2, 201–211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hellings, N.; Raus, J.; Stinissen, P. T-cell based immunotherapy in multiple sclerosis: Induction of regulatory immune networks by T-cell vaccination. Expert Rev. Clin. Immunol. 2006, 2, 705–716. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, Y.; Fang, L.; Peng, L.; Qiu, W. TLR9 and its signaling pathway in multiple sclerosis. J. Neurol. Sci. 2017, 373, 95–99. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Willekens, B.; Cools, N. Beyond the magic bullet: Current progress of therapeutic vaccination in multiple sclerosis. CNS Drugs 2018, 32, 401–410. [Google Scholar] [CrossRef] [Scilit]
- Skaper, S.D. Chapter 4—Oligodendrocyte precursor cells as a therapeutic target for demyelinating diseases, Prog. Brain Res. 2019, 245, 119–144. [Google Scholar] [CrossRef] [Scilit]
- Gholamzad, M.; Ebtekar, M.; Ardestani, M.S.; Azimi, M.; Mahmodi, Z.; Mousavi, M.J.; Aslani, S. A comprehensive review on the treatment approaches of multiple sclerosis: Currently and in the future. Inflamm. Res. 2019, 68, 25–38. [Google Scholar] [CrossRef] [Scilit]
- Derfuss, T. Personalized medicine in multiple sclerosis: Hope or reality? BMC Medicine. 2012, 10, 116. [Google Scholar] [CrossRef] [Scilit]
- Lassmann, H. Pathogenic mechanisms associated with different clinical courses of multiple sclerosis. Front. Immunol. 2019, 9, 3116. [Google Scholar] [CrossRef] [Scilit]
- Xie, Z.-X.; Zhang, H.-L.; Wu, X.-J.; Zhu, J.; Ma, D.-H.; Jin, T. Role of the immunogenic and tolerogenic subsets of dendritic cells in multiple sclerosis. Mediat. Inflamm. 2015, 20, 513295. [Google Scholar] [CrossRef] [Scilit]
- Rostami, A.; Ciric, B. Role of Th17 cells in the pathogenesis of CNS inflammatory demyelination. J. Neurol. Sci. 2013, 333, 76–87. [Google Scholar] [CrossRef] [Scilit]
- Baldassari, L.E.; Fox, R.J. Therapeutic advances and challenges in the treatment of progressive multiple sclerosis. Drugs 2018, 78, 1549–1566. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Magliozzi, R.; Howell, O.; Vora, A.; Serafini, B.; Nicholas, R.; Puopolo, M.; Reynolds, R.; Aloisi, F. Meningeal B-cell follicles in secondary progressive multiple sclerosis associate with early onset of disease and severe cortical pathology. Brain 2007, 130, 1089–1104. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dolati, S.; Babaloo, Z.; Jadidi-Niaragh, F.; Ayromlou, H.; Sadreddini, S.; Yousefi, M. Multiple sclerosis: Therapeutic applications of advancing drug delivery systems. Biomed. Pharmacother. 2017, 86, 343–353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wucherpfennig, K.W.; Strominger, J.L. Molecular mimicry in T cell-mediated autoimmunity: Viral peptides activate human T cell clones specific for myelin basic protein. Cell 1995, 80, 695–705. [Google Scholar] [CrossRef] [Scilit]
- Fujinami, R.S.; von Herrath, M.G.; Christen, U.; Whitton, J.L. Molecular mimicry, bystander activation, or viral persistence: Infections and autoimmune disease. Clin. Microbiol. Rev. 2006, 19, 80–94. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, T.-S.; Shin, E.-C. The activation of bystander CD8+ T cells and their roles in viral infection. Exp. Mol. Med. 2019, 51, 154. [Google Scholar] [CrossRef] [Scilit]
- Giacomini, P.S.; Bar-Or, A. Antigen-specific therapies in multiple sclerosis. Expert Opin. Emerg. Drugs 2009, 14, 551–560. [Google Scholar] [CrossRef] [Scilit]
- Szczepanik, M. Mechanisms of immunological tolerance to the antigens of the central nervous system. Skin-induced tolerance as a new therapeutic concept. J. Physiol. Pharmacol. 2011, 62, 159–165. [Google Scholar]
- Hellings, N.; Raus, J.; Stinissen, P. T-cell vaccination in multiple sclerosis: Update on clinical application and mode of action. Autoimmun. Rev. 2004, 3, 267–275. [Google Scholar] [CrossRef] [Scilit]
- Irvine, D.J.; Hanson, M.C.; Rakhra, K.; Tokatlian, T. Synthetic nanoparticles for vaccines and immunotherapy. Chem. Rev. 2015, 115, 11109–11146. [Google Scholar] [CrossRef] [Scilit]
- Selter, R.C.; Hemmer, B. Update on immunopathogenesis and immunotherapy in multiple sclerosis. Immunotargets Ther. 2013, 2, 21–30. [Google Scholar] [CrossRef] [Scilit]
- Lim, E.T.; Giovannoni, G. Immunopathogenesis and immunotherapeutic approaches in multiple sclerosis. Expert Rev. Neurother. 2005, 5, 379–390. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grigoriadis, N.; van Pesch, V. A basic overview of multiple sclerosis immunopathology. Eur. J. Neurol. 2015, 22, 3–13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sie, C.; Korn, T.; Mitsdoerffer, M. Th17 cells in central nervous system autoimmunity. Exp. Neurol. 2014, 262, 18–27. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- García-González, P.; Ubilla-Olguín, G.; Catalán, D.; Schinnerling, K.; Aguillón, J.C. Tolerogenic dendritic cells for reprogramming of lymphocyte responses in autoimmune diseases. Autoimmun. Rev. 2016, 15, 1071–1080. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- AGreenfield, L.; Hauser, S.L. B Cell therapy for multiple sclerosis: Entering an era. Ann. Neurol. 2018, 83, 13–26. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lu, L.-F.; Rudensky, A. Molecular orchestration of differentiation and function of regulatory T cells. Genes Dev. 2009, 23, 1270–1282. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gregori, S.; Goudy, K.S.; Roncarolo, M.G. The cellular and molecular mechanisms of immuno-suppression by human type 1 regulatory T cells. Front. Immunol. 2012, 3, 30. [Google Scholar] [CrossRef] [Scilit]
- Lu, W.; Chen, S.; Lai, C.; Lai, M.; Fang, H.; Dao, H.; Kang, J.; Fan, J.; Guo, W.; Fu, L.; et al. Suppression of HIV replication by CD8(+) regulatory T cells in elite controllers. Front. Immunol. 2016, 7, 134. [Google Scholar] [CrossRef] [Scilit]
- Vuddamalay, Y.; van Meerwijk, J.P.M. CD28- and CD28lowCD8+ regulatory T cells: Of mice and men. Front. Immunol. 2017, 8, 31. [Google Scholar] [CrossRef] [Scilit]
- Milo, R. Therapeutic strategies targeting B-cells in multiple sclerosis. Autoimmun. Rev. 2016, 15, 714–718. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Y.; Salter, A.; Wallström, E.; Cutter, G.; Stüve, O. Evolution of clinical trials in multiple sclerosis. Ther. Adv. Neurol. Disord. 2019, 12, 1–14. [Google Scholar] [CrossRef] [Scilit]
- Dargahi, N.; Katsara, M.; Tselios, T.; Androutsou, M.-E.; de Courten, M.; Matsoukas, J.; Apostolopoulos, V. Multiple sclerosis: Immunopathology and treatment update. Brain Sci. 2017, 7, 78. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gentile, A.; Musella, A.; de Vito, F.; Rizzo, F.R.; Fresegna, D.; Bullitta, S.; Vanni, V.; Guadalupi, L.; Bassi, M.S.; Buttari, F.; et al. Immunomodulatory effects of exercise in experimental multiple sclerosis. Front. Immunol. 2019, 10, 2197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pasquier, R.A.D.; Pinschewer, D.D.; Merkler, D. Immunological mechanism of action and clinical profile of disease-modifying treatments in multiple sclerosis. CNS Drugs 2014, 28, 535–558. [Google Scholar] [CrossRef] [Scilit]
- Tapeinos, C.; Battaglini, M.; Ciofani, G. Advances in the design of solid lipid nanoparticles and nanostructured lipid carriers for targeting brain diseases. J. Control. Release 2017, 264, 306–332. [Google Scholar] [CrossRef] [Scilit]
- Cross, A.H.; Naismith, R.T. Established and novel disease-modifying treatments in multiple sclerosis. J. Intern. Med. 2014, 275, 350–363. [Google Scholar] [CrossRef] [Scilit]
- Piehl, F. A changing treatment landscape for multiple sclerosis: Challenges and opportunities. J. Intern. Med. 2014, 275, 364–381. [Google Scholar] [CrossRef] [Scilit]
- Wingerchuk, D.M.; Carter, J.L. Multiple Sclerosis: Current and Emerging Disease-Modifying Therapies and Treatment Strategies. Mayo Clin. Proc. 2014, 89, 225–240. [Google Scholar] [CrossRef] [Scilit]
- Tramacere, I.; del Giovane, C.; Salanti, G.; D’Amico, R.; Pacchetti, I.; Filippini, G. Immunomodulators and immunosuppressants for relapsing-remitting multiple sclerosis: A network meta-analysis. Cochrane Database Syst. Rev. 2015, 9, CD011381. [Google Scholar] [CrossRef] [Scilit]
- Wraith, D.C. The future of immunotherapy: A 20-year perspective. Front. Immunol. 2017, 8, 1668. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- D’Amico, E.; Patti, F.; Zanghì, A.; Zappia, M. A personalized approach in progressive multiple sclerosis: The current status of disease modifying therapies (DMTs) and future perspectives. Int. J. Mol. Sci. 2016, 17, 1725. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ciotti, J.R.; Cross, A.H. Disease-Modifying Treatment in Progressive Multiple Sclerosis. Curr. Treat. Options Neurol. 2018, 20, 12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lassmann, H. Targets of therapy in progressive MS. Mult. Scler. 2017, 23, 1593–1599. [Google Scholar] [CrossRef] [Scilit]
- Novartis Receives FDA Approval for Mayzent® (Siponimod), the First Oral Drug to Treat Secondary Progressive MS with Active Disease. Available online: https://novartis.gcs-web.com/Novartis-receives-FDA-approval-for-Mayzent-siponimod-the-first-oral-drug-to-treat-secondary-progressive-MS-with-active-disease?_ga=2.241998658.1110943223.1587297344-1758107691.1587297344 (accessed on 14 April 2020).
- Zeposia (Ozanimod). Available online: https://multiplesclerosisnewstoday.com/zeposia-ozanimod-rpc1063-rrms/ (accessed on 14 April 2020).
- Cladribine. Available online: https://en.wikipedia.org/wiki/Cladribine (accessed on 14 April 2020).
- Wildner, P.; Selmaj, K.W. Multiple sclerosis: Skin-induced antigen-specific immune tolerance. J. Neuroimmunol. 2017, 311, 49–58. [Google Scholar] [CrossRef] [Scilit]
- Sospedra, M.; Martin, R. Antigen-Specific Therapies in Multiple Sclerosis. Int. Rev. Immunol. 2005, 24, 393–413. [Google Scholar] [CrossRef] [Scilit]
- Blanchfield, J.L. Antigen-specific tolerogenic vaccines inhibit autoimmune disease in a rodent model of multiple sclerosis. Ph.D. Thesis, The Faculty of the Department of Microbiology and Immunology Brody School of Medicine at East Carolina University, Greenville, USA, 2010. [Google Scholar]
- Pickens, C.J.; Christopher, M.A.; Leon, M.A.; Pressnall, M.M.; Johnson, S.N.; Thati, S.; Sullivan, B.P.; Berkland, C. Antigen-drug conjugates as a novel therapeutic class for the treatment of antigen-specific autoimmune disorders. Mol. Pharm. 2019, 16, 2452–2461. [Google Scholar] [CrossRef] [Scilit]
- Chunsong, Y.; Jingchao, X.; Meng, L.; Myunggi, A.; Haipeng, L. Bioconjugate strategies for the induction of antigen-specific tolerance in autoimmune diseases. Bioconjug. Chem. 2018, 29, 29719–29732. [Google Scholar] [CrossRef] [Scilit]
- Mannie, M.D.; Curtis, A.D. II Tolerogenic vaccines for multiple sclerosis. Hum. Vac. Immunother. 2013, 9, 1032–1038. [Google Scholar] [CrossRef] [Scilit]
- Yannakakis, M.P.; Tzoupis, H.; Michailidou, E.; Mantzourani, E.; Simal, C.; Tselios, T. Molecular dynamics at the receptor level of immunodominant myelin oligodendrocyte glycoprotein 35–55 epitope implicated in multiple sclerosis. J. Mol. Graph. Model. 2016, 68, 78–86. [Google Scholar] [CrossRef] [Scilit]
- Lutterotti, A.; Martin, R. Antigen-specific tolerization approaches in multiple sclerosis. Expert Opin. Investig. Drugs 2014, 23, 9–20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wraith, D. Antigen-specific immunotherapy. Nature 2016, 530, 422–423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Spence, A.; Klementowicz, J.E.; Bluestone, J.A.; Tang, Q. Targeting Treg signaling for the treatment of autoimmune diseases. Curr. Opin. Immunol. 2015, 37, 11–20. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sabatos-Peyton, C.A.; Verhagen, J.; Wraith, D.C. Antigen-specific immunotherapy of autoimmune and allergic diseases. Curr. Opin. Immunol. 2010, 22, 609–615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Steinman, L. The re-emergence of antigen-specific tolerance as a potential therapy for MS. Mult. Scler. J. 2015, 21, 1223–1238. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cappellano, G.; Comi, C.; Chiocchetti, A.; Dianzani, U. Exploiting PLGA-based biocompatible nanoparticles for next-generation tolerogenic vaccines against autoimmune disease. Int. J. Mol. Sci. 2019, 20, 204. [Google Scholar] [CrossRef] [Scilit]
- Vanderlugt, C.L.; Miller, S.D. Epitope spreading inimmune-mediated diseases: Implications for immunotherapy. Nat. Rev. Immunol. 2002, 2, 85–95. [Google Scholar] [CrossRef] [Scilit]
- Miller, S.D.; Turley, D.M.; Podojil, J.R. Antigen-specific tolerance strategies for the prevention and treatment of autoimmune disease. Nat. Rev. Immunol. 2007, 7, 665–677. [Google Scholar] [CrossRef] [Scilit]
- Lutterotti, A.; Sospedra, M.; Martin, R. Antigen-specific therapies in MS—Current concepts and novel approaches. J. Neurol. Sci. 2008, 274, 18–22. [Google Scholar] [CrossRef] [Scilit]
- Bielekova, B.; Goodwin, B.; Richert, N.; Cortese, I.; Kondo, T.; Afshar, G.; Grani, B.; Eaton, J.; Antel, J.; Frank, J.A.; et al. Encephalitogenic potential of the myelin basic protein peptide (amino acids 83–99) in multiple sclerosis: Results of a phase II clinical trial with an altered peptide ligand. Nat. Med. 2000, 6, 1167–1175. [Google Scholar] [CrossRef] [Scilit]
- Turley, D.M.; Miller, S.D. Prospects for antigen-specific tolerance based therapies for the treatment of multiple sclerosis, Results Probl. Cell Differ. 2010, 51, 217–235. [Google Scholar] [CrossRef] [Scilit]
- Constantinescu, C.S.; Farooqi, N.; O’Brien, K.; Gran, B. Experimental autoimmune encephalomyelitis (EAE) as a model for multiple sclerosis (MS). Br. J. Pharmacol. 2011, 164, 1079–1106. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fletcher, J.M.; Lalor, S.J.; Sweeney, C.M.; Tubridy, N.; Mills, K.H. T cells in multiple sclerosis and experimental autoimmune encephalomyelitis. Clin. Exp. Immunol. 2010, 162, 1–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Libbey, J.E.; Fujinami, R.S. Experimental autoimmune encephalomyelitis as a testing paradigm for adjuvants and vaccines. Vaccine 2011, 29, 3356–3362. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tabansky, I.; Keskin, D.B.; Watts, D.; Petzold, C.; Funaro, M.; Sands, W.; Wright, P.; Yunis, E.J.; Najjar, S.; Diamond, B.; et al. Targeting DEC-205−DCIR2+ dendritic cells promotes immunological tolerance in proteolipid protein-induced experimental autoimmune encephalomyelitis. Mol. Med. 2018, 24, 17. [Google Scholar] [CrossRef] [Scilit]
- Huang, X.; Lu, H.W.Q. The mechanisms and applications of T cell vaccination for autoimmune diseases: A comprehensive review. Clinic. Rev. Allerg. Immunol. 2014, 47, 219–233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grau-López, L.; Raïch, D.; Ramo-Tello, C.; Naranjo-Gómez, M.; Dàvalos, A.; Pujol-Borrell, R.; Borràs, F.E.; Martínez-Cáceres, E. Myelin peptides in multiple sclerosis. Autoimmun. Rev. 2009, 8, 650–653. [Google Scholar] [CrossRef] [Scilit]
- Kuchroo, V.K.; Anderson, A.C.; Waldner, H.; Munder, M.; Bettelli, E.; Nicholson, L.B. T cell response in experimental autoimmune encephalomyelitis (EAE): Role of Self and Cross-Reactive Antigens in Shaping, Tuning, and Regulating the Autopathogenic T Cell Repertoire. Annu. Rev. Immunol. 2002, 20, 101–123. [Google Scholar] [CrossRef] [Scilit]
- Matsoukas, J.; Apostolopoulos, V.; Kalbacher, H.; Papini, A.-M.; Tselios, T.; Chatzantoni, K.; Biagioli, T.; Lolli, F.; Deraos, S.; Papathanassopoulos, P.; et al. Design and synthesis of a novel potent myelin basic protein epitope 87-99 cyclic analogue: Enhanced stability and biological properties of mimics render them a potentially new class of immunomodulators. J. Med. Chem. 2005, 48, 1470–1480. [Google Scholar] [CrossRef] [Scilit]
- Reindl, M.; Waters, P. Myelin oligodendrocyte glycoprotein antibodies in neurological disease. Nat. Rev. Neurol. 2019, 15, 89–102. [Google Scholar] [CrossRef] [Scilit]
- Kaushansky, N.; Eisenstein, M.; Zilkha-Falb, R.; Ben-Nun, A. The myelin-associated oligodendrocytic basic protein (MOBP) as a relevant primary target autoantigen in multiple sclerosis. Autoimmun. Rev. 2010, 9, 233–236. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Androutsou, M.E.; Tapeinou, A.; Vlamis-Gardikas, A.; Tselios, T. Myelin oligodendrocyte glycoprotein and multiple sclerosis. Med. Chem. 2018, 14, 120–128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tselios, T.; Aggelidakis, M.; Tapeinou, A.; Tseveleki, V.; Kanistras, I.; Gatos, D.; Matsoukas, J. Rational design and synthesis of altered peptide ligands based on human myelin oligodendrocyte glycoprotein 35–55 epitope: Inhibition of chronic experimental autoimmune encephalomyelitis in mice. Molecules 2014, 19, 17968–17984. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Deraos, G.; Kritsi, E.; Matsoukas, M.-T.; Christopoulou, K.; Kalbacher, H.; Zoumpoulakis, P.; Apostolopoulos, V.; Matsoukas, J. Design of linear and cyclic mutant analogues of dirucotide peptide (MBP82–98) against multiple sclerosis: Conformational and binding studies to MHC Class II. Brain Sci. 2018, 8, 213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tapeinou, A.; Giannopoulou, E.; Hansen, C.S.B.E.; Kalofonos, H.; Apostolopoulosd, V.; Vlamis-Gardikas, A.; Tselios, T. Design, synthesis and evaluation of an anthraquinone derivative conjugated to myelin basic protein immunodominant (MBP85-99) epitope: Towards selective immunosuppression. Eur. J. Med. Chem. 2018, 143, 621–631. [Google Scholar] [CrossRef] [Scilit]
- Yannakakis, M.-P.; Simal, C.; Tzoupis, H.; Rodi, M.; Dargahi, N.; Prakash, M.; Mouzaki, A.; Platts, J.A.; Apostolopoulos, V.; Tselios, T.V. Design and synthesis of non-peptide mimetics mapping the immunodominant myelin basic protein (MBP83–96) epitope to function as T-cell receptor antagonists. Int. J. Mol. Sci. 2017, 18, 1215. [Google Scholar] [CrossRef] [Scilit]
- Correale, J.; Farez, M.; Gilmore, W. Vaccines for multiple sclerosis: Progress to date. CNS Drugs 2008, 22, 175–198. [Google Scholar] [CrossRef] [Scilit]
- Mantzourani, E.D.; Platts, J.A.; Brancale, A.; Mavromoustakos, T.M.; Tselios, T.V. Molecular dynamics at the receptor level of immunodominant myelin basic protein epitope 87–99 implicated in multiple sclerosis and its antagonists altered peptide ligands: Triggering of immune response. J. Mol. Graph. Model. 2007, 26, 471–481. [Google Scholar] [CrossRef] [Scilit]
- Kaushansky, N.; de Rosbo, N.K.; Zilkha-Falb, R.; Yosef-Hemo, R.; Cohen, L.; Ben-Nun, A. ‘Multi-epitope-targeted’ immune-specific therapy for a multiple sclerosis-like disease via engineered multi-epitope protein is superior to peptides. PLoS ONE 2011, 6, e27860. [Google Scholar] [CrossRef] [Scilit]
- Kaushansky, N.; Kaminitz, A.; Allouche-Arnon, H.; Ben-Nun, A. Modulation of MS-like disease by a multi epitope protein is mediated by induction of CD11c+ CD11b+ Gr1+ myeloid-derived dendritic cells. J. Neuroimmunol. 2019, 333, 476953. [Google Scholar] [CrossRef] [Scilit]
- Moorman, C.D.; Curtis, A.D., 2nd; Bastian, A.G.; Elliott, S.E.; Mannie, M.D. A GMCSF-Neuroantigen Tolerogenic Vaccine Elicits Systemic Lymphocytosis of CD4+ CD25high FOXP3+ Regulatory T Cells in Myelin-Specific TCR Transgenic Mice Contingent Upon Low-Efficiency T Cell Antigen Receptor Recognition. Front. Immunol. 2019, 9, 3119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mannie, M.D.; Blanchfield, J.L.; Islam, S.M.T.; Abbott, D.J. Cytokine-neuroantigen fusion proteins as a new class of tolerogenic, therapeutic vaccines for treatment of inflammatory demyelinating disease in rodent models of multiple sclerosis. Front. Immunol. 2012, 3, 255. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abbott, D.J.; Blanchfield, J.L.; Martinson, D.A.; Russell, S.C.; Taslim, N.; Curtis, A.D.; Mannie, M.D. Neuroantigen-specific, tolerogenic vaccines: GMCSF is a fusion partner that facilitates tolerance rather than immunity to dominant self-epitopes of myelin in murine models of experimental autoimmune encephalomyelitis (EAE). BMC Immunol. 2011, 12, 72. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Blanchfield, J.L.; Mannie, M.D. A GMCSF-neuroantigen fusion protein is a potent tolerogen in experimental autoimmune encephalomyelitis (EAE) that is associated with efficient targeting of neuroantigen to APC. J. Leukoc. Biol. 2010, 87, 509–521. [Google Scholar] [CrossRef] [Scilit]
- Petzold, C.; Schallenberg, S.; Stern, J.N.H.; Kretschmer, K. Targeted antigen delivery to DEC-205+ dendritic cells for tolerogenic vaccination. Rev. Diabet. Stud. 2012, 9, 305–318. [Google Scholar] [CrossRef] [Scilit]
- Idoyaga, J.; Fiorese, C.; Zbytnuik, L.; Lubkin, A.; Miller, J.; Malissen, B.; Mucida, D.; Merad, M.; Steinman, R.M. Specialized role of migratory dendritic cells in peripheral tolerance induction. J. Clin. Investig. 2013, 123, 844–854. [Google Scholar] [CrossRef] [Scilit]
- Stern, J.N.H.; Keskin, D.B.; Kato, Z.; Waldner, H.; Schallenberg, S.; Anderson, A.; von Boehmer, H.; Kretschmer, K.; Strominger, J.L. Promoting tolerance to proteolipid protein-induced experimental autoimmune encephalomyelitis through targeting dendritic cells. Proc. Natl. Acad. Sci. USA 2010, 107, 17280–17285. [Google Scholar] [CrossRef] [Scilit]
- Ring, S.; Maas, M.; Nettelbeck, D.M.; Enk, A.H.; Mahnke, K. Targeting of autoantigens to DEC205+ dendritic cells in vivo suppresses experimental allergic encephalomyelitis in mice. J. Immunol. 2013, 191, 2938–2947. [Google Scholar] [CrossRef] [Scilit]
- Kasagi, S.; Wang, D.; Zhang, P.; Zanvit, P.; Chen, H.; Zhang, D.; Li, J.; Che, L.; Maruyama, T.; Nakatsukasa, H.; et al. Combination of apoptotic T cell induction and self-peptide administration for therapy of experimental autoimmune encephalomyelitis. EBioMedicine 2019, 44, 50–59. [Google Scholar] [CrossRef] [Scilit]
- Clemente-Casares, X.; Tsai, S.; Yang, Y.; Santamaria, P. Peptide-MHC-based nanovaccines for the treatment of autoimmunity: A “one size fits all” approach? J. Mol. Med. 2011, 89, 733–742. [Google Scholar] [CrossRef] [Scilit]
- Offner, H.; Sinha, S.; Wang, C.; Burrows, G.G.; Vandenbark, A.A. Recombinant T-cell receptor ligands: Immunomodulatory, neuroprotective and neuroregenerative effects suggest application as therapy for multiple sclerosis. Rev. Neurosci. 2008, 19, 327–339. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sinha, S.; Subramanian, S.; Emerson-Webber, A.; Lindner, M.; Burrows, G.G.; Grafe, M.; Linington, C.; Vandenbark, A.A.; Bernard, C.C.A.; Offner, H. Recombinant TCR ligand reverses clinical signs and CNS damage of EAE induced by recombinant human MOG. J. Neuroimmune Pharmacol. 2010, 5, 231–239. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gong, Y.; Wang, Z.; Liang, Z.; Duan, H.; Ouyang, L.; Yu, Q.; Xu, Z.; Shen, G.; Weng, X.; Wu, X. Soluble MOG35-55/I-Ab Dimers Ameliorate Experimental Autoimmune Encephalomyelitis by Reducing Encephalitogenic T Cells. PLoS ONE 2012, 7, e47435. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vandenbark, A.A.; Rich, C.; Mooney, J.; Zamora, A.; Wang, C.; Huan, J.; Fugger, L.; Offner, H.; Jones, R.; Burrows, G.G. Recombinant TCR ligand induces tolerance to myelin oligodendrocyte glycoprotein 35-55 peptide and reverses clinical and histological signs of chronic experimental autoimmune encephalomyelitis in HLA-DR2 transgenic mice. J. Immunol. 2003, 171, 127–133. [Google Scholar] [CrossRef] [Scilit]
- White, D.R.; Khedri, Z.; Kiptoo, P.; Siahaan, T.J.; Tolbert, T.J. Synthesis of a bifunctional peptide inhibitor–IgG1 Fc fusion that suppresses experimental autoimmune encephalomyelitis. Bioconjug. Chem. 2017, 28, 1867–1877. [Google Scholar] [CrossRef] [Scilit]
- Ridwan, R.; Kiptoo, P.; Kobayashi, N.; Weir, S.; Hughes, M.; Williams, T.; Soegianto, R.; Siahaan, T.J. Antigen-specific suppression of experimental autoimmune encephalomyelitis by a novel bifunctional peptide inhibitor: Structure optimization and pharmacokinetics. JPET 2010, 332, 1136–1145. [Google Scholar] [CrossRef] [Scilit]
- Badawi, A.H.; Siahaan, T.J. Suppression of MOG- and PLP-induced experimental autoimmune encephalomyelitis using a novel multivalent bifunctional peptide inhibitor. J. Neuroimmunol. 2013, 263, 20–27. [Google Scholar] [CrossRef] [Scilit]
- Majewska, M.; Zając, K.; Srebro, Z.; Sura, P.; Książek, L.; Zemelka, M.; Szczepanik, M. Epicutaneous immunization with myelin basic protein protects from the experimental autoimmune encephalomyelitis. Pharmacol. Rep. 2007, 59, 74–79. [Google Scholar]
- Szczepanik, M.; Tutaj, M.; Bryniarski, K.; Dittel, B.N. Epicutaneously induced TGF-h-dependent tolerance inhibits experimental autoimmune encephalomyelitis. J. Neuroimmunol. 2005, 164, 105–114. [Google Scholar] [CrossRef] [Scilit]
- Tutaj, M.; Szczepanik, M. Epicutaneous (EC) immunization with myelin basic protein (MBP) induces TCRabþ CD4þ CD8þ double positive suppressor cells that protect from experimental autoimmune encephalomyelitis (EAE). J. Autoimmun. 2007, 28, 208–215. [Google Scholar] [CrossRef] [Scilit]
- Li, H.; Zhang, G.-X.; Chen, Y.; Xu, H.; Fitzgerald, D.C.; Zhao, Z.; Rostami, A. CD11c+CD11b+ Dendritic cells play an important role in intravenous tolerance and the suppression of experimental autoimmune encephalomyelitis. J. Immunol. 2008, 181, 2483–2493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lourbopoulos, A.; Deraos, G.; Matsoukas, M.-T.; Touloumi, O.; Giannakopoulou, A.; Kalbacher, H.; Grigoriadis, N.; Apostolopoulos, V.; Matsoukas, J. Cyclic MOG35–55 ameliorates clinical and neuropathological features of experimental autoimmune encephalomyelitis, Bioorgan. Med. Chem. 2017, 25, 4163–4174. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Streeter, H.B.; Rigden, R.; Martin, K.F.; Scolding, N.J.; Wraith, D.C. Preclinical development and first-in-human study of ATX-MS-1467 for immunotherapy of MS. Neurol. Neuroimmunol. Neuroinflamm. 2015, 2, e93. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Billetta, R.; Ghahramani, N.; Morrow, O.; Prakken, B.; de Jong, H.; Meschter, C.; Lanza, P.; Albani, S. Epitope-specific immune tolerization ameliorates experimental autoimmune encephalomyelitis. Clin. Immunol. 2012, 145, 94–101. [Google Scholar] [CrossRef] [Scilit]
- Peron, J.P.S.; Yang, K.; Chen, M.-L.; Brandao, W.N.; Basso, A.S.; Commodaro, A.G.; Weiner, H.L.; Rizzo, L.V. Oral tolerance reduces Th17 cells as well as the overall inflammation in the central nervous system of EAE mice. J. Neuroimmunol. 2010, 227, 10–17. [Google Scholar] [CrossRef] [Scilit]
- Song, F.; Guan, Z.; Gienapp, I.E.; Shawler, T.; Benson, J.; Whitacre, C.C. The thymus plays a role in oral tolerance in experimental autoimmune encephalomyelitis. J. Immunol. 2006, 177, 1500–1509. [Google Scholar] [CrossRef] [Scilit]
- Deraos, G.; Rodi, M.; Kalbacher, H.; Chatzantoni, K.; Karagiannis, F.; Synodinos, L.; Plotas, P.; Papalois, A.; Dimisianos, N.; Papathanasopoulos, P.; et al. Properties of myelin altered peptide ligand cyclo(8–99)(Ala91,Ala96) MBP87-99 render it a promising drug lead for immunotherapy of multiple sclerosis. Eur. J. Med.Chem. 2015, 101, 13–23. [Google Scholar] [CrossRef] [Scilit]
- Islam, S.M.T.; Curtis, A.D., 2nd; Taslim, N.; Wilkinson, D.S.; Mannie, M.D. GM-CSF-neuroantigen fusion proteins reverse experimental autoimmune encephalomyelitis and mediate tolerogenic activity in adjuvant-primed environments: Association with inflammation-dependent, inhibitory antigen presentation. J. Immunol. 2014, 193, 2317–2329. [Google Scholar] [CrossRef] [Scilit]
- Mannie, M.D.; Clayson, B.A.; Buskirk, E.J.; DeVine, J.L.; Hernandez, J.J.; Abbott, D.J. IL-2/Neuroantigen fusion proteins as antigen-specific tolerogens in experimental autoimmune encephalomyelitis (EAE): Correlation of T cell-mediated antigen presentation and tolerance induction. J. Immunol. 2007, 178, 2835–2843. [Google Scholar] [CrossRef] [Scilit]
- Link, J.M.; Rich, C.M.; Korat, M.; Burrows, G.G.; Offner, H.; Vandenbark, A.A. Monomeric DR2/MOG-35--55 recombinant TCR ligand treats relapses of experimental encephalomyelitis in DR2 transgenic mice. Clin. Immunol. 2007, 123, 95–104. [Google Scholar] [CrossRef] [Scilit]
- Huan, J.; Subramanian, S.; Jones, R.; Rich, C.; Link, J.; Mooney, J.; Bourdette, D.N.; Vandenbark, A.A.; Burrows, G.G.; Offner, H. Monomeric recombinant TCR ligand reduces relapse rate and severity of experimental autoimmune encephalomyelitis in SJL/J mice through cytokine switch. J. Immunol. 2004, 172, 4556–4566. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Offner, H.; Subramanian, S.; Wang, C.; Afentoulis, M.; Vandenbark, A.A.; Huan, J.; Burrows, G.G. Treatment of passive experimental autoimmune encephalomyelitis in SJL mice with a recombinant TCR ligand induces IL-13 and prevents axonal injury. J. Immunol. 2005, 175, 4103–4111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sinha, S.; Subramanian, S.; Proctor, T.M.; Kaler, L.J.; Grafe, M.; Dahan, R.; Huan, J.; Vandenbark, A.A.; Burrows, G.G.; Offner, H. A promising therapeutic approach for multiple sclerosis: Recombinant T-cell receptor ligands modulate experimental autoimmune encephalomyelitis by reducing interleukin-17 production and inhibiting migration of encephalitogenic cells into the CNS. J. Neurosci. 2007, 27, 12531–12539. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sinha, S.; Subramanian, S.; Miller, L.; Proctor, T.M.; Roberts, C.; Burrows, G.G.; Vandenbark, A.A.; Offner, H. Cytokine switch and bystander suppression of autoimmune responses to multiple antigens in experimental autoimmune encephalomyelitis by a single recombinant T-Cell receptor ligand. J. Neurosci. 2009, 29, 3816–3823. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sinha, S.; Miller, L.; Subramanian, S.; McCarty, O.; Proctor, T.; Meza-Romero, R.; Burrows, G.G.; Vandenbark, A.A.; Offner, H. Binding of recombinant T cell receptor ligands (RTL) to antigen presenting cells prevents upregulation of CD11b and inhibits T cell activation and transfer of experimental autoimmune encephalomyelitis. J. Neuroimmunol. 2010, 225, 52–61. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, C.; Gold, B.G.; Kaler, L.J.; Yu, X.; Afentoulis, M.E.; Burrows, G.G.; Vandenbark, A.A.; Bourdette, D.N.; Offner, H. Antigen-specific therapy promotes repair of myelin and axonal damage in established EAE. J. Neurochem. 2006, 98, 1817–1827. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Badawi, A.H.; Kiptoo, P.; Siahaan, T.J. Immune tolerance induction against experimental Autoimmune Encephalomyelitis (EAE) Using A New PLP-B7AP Conjugate that simultaneously targets B7/CD28 costimulatory signal and TCR/MHC-II signal. J. Mult. Scler. (Foster City) 2015, 2, 1000131. [Google Scholar]
- Badawi, A.H.; Kiptoo, P.; Wang, W.-T.; Choi, I.-Y.; Lee, P.; Vines, C.M.; Siahaan, T.J. Suppression of EAE and prevention of blood-brain barrier breakdown after vaccination with novel bifunctional peptide inhibitor. Neuropharmacology 2012, 62, 1874–1881. [Google Scholar] [CrossRef] [Scilit]
- Kobayashi, N.; Kobayashi, H.; Gu, L.; Malefyt, T.; Siahaan, T.J. Antigen-specific suppression of experimental autoimmune encephalomyelitis by a novel bifunctional peptide inhibitor. JPET 2007, 322, 879–886. [Google Scholar] [CrossRef] [Scilit]
- Kobayashi, N.; Kiptoo, P.; Kobayashi, H.; Ridwan, R.; Brocke, S.; Siahaan, T.J. Prophylactic and therapeutic suppression of experimental autoimmune encephalomyelitis by a novel bifunctional peptide inhibitor. Clin. Immunol. 2008, 129, 69–79. [Google Scholar] [CrossRef] [Scilit]
- Kiptoo, P.; Büyüktimkin, B.; Badawi, A.H.; Stewart, J.; Ridwan, R.; Siahaan, T.J. Controlling immune response and demyelination using highly potent bifunctional peptide inhibitors in the suppression of experimental autoimmune encephalomyelitis. Clin. Exp. Immunol. 2012, 172, 23–36. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fissolo, N.; Montalban, X.; Comabella, M. DNA vaccination techniques. Methods Mol. Biol. 2016, 1304, 39–50. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garren, H. DNA vaccines for autoimmune diseases. Expert Rev. Vaccines 2009, 8, 1195–1203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fontoura, P.; Garren, H.; Steinman, L. Antigen-specific therapies in multiple sclerosis: Going beyond proteins and peptides. Int. Rev. Immunol. 2005, 24, 415–446. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fissolo, N.; Montalban, X.; Comabella, M. DNA-based vaccines for multiple sclerosis: Current status and future directions. Clin. Immunol. 2012, 142, 76–83. [Google Scholar] [CrossRef] [Scilit]
- Stuve, O.; Cravens, P.; Eagar, T.N. DNA-based vaccines: The future of multiple sclerosis therapy? Expert Rev. Neurother. 2008, 8, 351–360. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jakimovski, D.; Weinstock-Guttman, B.; Ramanathan, M.; Dwyer, M.G.; Zivadinov, R. Infections, vaccines and autoimmunity: A multiple sclerosis perspective. Vaccines 2020, 8, 50. [Google Scholar] [CrossRef] [Scilit]
- Garren, H.; Ruiz, P.J.; Watkins, T.A.; Fontoura, P.; Nguyen, L.-V.T.; Estline, E.R.; Hirschberg, D.L.; Steinman, L. Combination of gene delivery and DNA vaccination to protect from and reverse Th1 autoimmune disease via deviation to the Th2 pathway. Immunity 2001, 15, 15–22. [Google Scholar] [CrossRef] [Scilit]
- Wefer, J.; Harris, R.A.; Lobell, A. Protective DNA vaccination against experimental autoimmune encephalomyelitis is associated with induction of IFNh. J. Neuroimmunol. 2004, 149, 66–76. [Google Scholar] [CrossRef] [Scilit]
- Schif-Zuck, S.; Wildbaum, G.; Karin, N. Coadministration of plasmid DNA constructs encoding an encephalitogenic determinant and IL-10 elicits regulatory T cell-mediated protective immunity in the central nervous system. J. Immunol. 2006, 177, 8241–8247. [Google Scholar] [CrossRef] [Scilit]
- Lobell, A.; Weissert, R.; Eltayeb, S.; de Graaf, K.L.; Wefer, J.; Storch, M.K.; Lassmann, H.; Wigzell, H.; Olsson, T. Suppressive DNA vaccination in myelin oligodendrocyte glycoprotein peptide-induced experimental autoimmune encephalomyelitis involves a T1-biased immune response. J. Immunol. 2003, 170, 1806–1813. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Andersson, A.; Isaksson, M.; Wefer, J.; Norling, A.; Flores-Morales, A.; Rorsman, F.; Kämpe, O.; Harris, R.A.; Lobell, A. Impaired autoimmune T helper 17 cell responses following DNA vaccination against rat experimental autoimmune encephalomyelitis. PLoS ONE 2008, 3, e3682. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kang, Y.; Sun, Y.; Zhang, J.; Gao, W.; Kang, J.; Wang, Y.; Wang, B.; Xia, G. Treg cell resistance to apoptosis in DNA vaccination for experimental autoimmune encephalomyelitis treatment. PLoS ONE 2012, 7, e49994. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Walczak, A.; Szymanska, B.; Selmaj, K. Differential prevention of experimental autoimmune encephalomyelitis with antigen-specific DNA vaccination. Clin. Neurol. Neurosurg. 2004, 106, 241–245. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, J.; Cao, X. Regulatory dendritic cells in autoimmunity: A comprehensive review. J. Autoimmun. 2015, 63, 1–12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Domogalla, M.P.; Rostan, P.V.; Raker, V.K.; Steinbrink, K. Tolerance through education: How tolerogenic dendritic cells shape immunity. Front. Immunol. 2017, 8, 1764. [Google Scholar] [CrossRef] [Scilit]
- Van Brussel, I.; Lee, W.P.; Rombouts, M.; Nuyts, A.H.; Heylen, M.; DeWinter, B.Y.; Cools, N.; Schrijvers, D.M. Tolerogenic dendritic cell vaccines to treat autoimmune diseases: Can the unattainable dream turn into reality? Autoimmun. Rev. 2014, 13, 138–150. [Google Scholar] [CrossRef] [Scilit]
- Flórez-Grau, G.; Zubizarreta, I.; Cabezón, R.; Villoslada, P.; Benitez-Ribas, D. Tolerogenic dendritic cells as a promising antigen-specific therapy in the treatment of multiple sclerosis and neuromyelitis optica from preclinical to clinical trials. Front. Immunol. 2018, 9, 1169. [Google Scholar] [CrossRef] [Scilit]
- Obregon, C.; Kumar, R.; Pascual, M.A.; Vassalli, G.; Golshayan, D. Update on dendritic cell-induced immunological and clinical tolerance. Front. Immunol. 2017, 8, 1514. [Google Scholar] [CrossRef] [Scilit]
- Derdelinckx, J.; Mansilla, M.J.; de Laere, M.; Lee, W.-P.; Navarro-Barriuso, J.; Wens, I.; Nkansah, I.; Daans, J.; de Reu, H.; Keliris, A.J.; et al. Clinical and immunological control of experimental autoimmune encephalomyelitis by tolerogenic dendritic cells loaded with MOG-encoding RNA. J. Neuroinflam. 2019, 16, 167. [Google Scholar] [CrossRef] [Scilit]
- Iberg, C.A.; Hawiger, D. Natural and induced tolerogenic dendritic cells. J. Immunol. 2020, 204, 733–744. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vandenbark, A.A.; Abulafia-Lapid, R. Autologous T-cell vaccination for multiple sclerosis: A perspective on progress. BioDrugs 2008, 22, 265–273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Volovitz, I.; Marmora, Y.; Mor, F.; Flügel, A.; Odoardi, F.; Eisenbach, L.; Cohen, I.R. T cell vaccination induces the elimination of EAE effector T cells: Analysis using GFP-transduced, encephalitogenic T cells. J. Autoimmun. 2010, 35, 135–144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Turley, D.M.; Miller, S.D. Peripheral tolerance induction using ethylenecarbodiimide-fixed APCs uses both direct and indirect mechanisms of antigen presentation for prevention of experimental autoimmune encephalomyelitis. J. Immunol. 2007, 178, 2212–2220. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Getts, D.R.; Turley, D.M.; Smith, C.E.; Harp, C.T.; McCarthy, D.; Feeney, E.M.; Getts, M.T.; Martin, A.J.; Luo, X.; Terry, R.R.; et al. Tolerance Induced by Apoptotic Antigen-Coupled Leukocytes is Induced by PD-L1+, IL-10-Producing Splenic Macrophages and Maintained by Tregs. J. Immunol. 2011, 187, 2405–2417. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pishesha, N.; Bilate, A.M.; Wibowo, M.C.; Huang, N.-J.; Lia, Z.; Deshycka, R.; Bousbaine, D.; Lia, H.; Pattersona, H.C.; Dougana, S.K.; et al. Engineered erythrocytes covalently linked to antigenic peptides can protect against autoimmune disease. Proc. Natl. Acad. Sci. USA 2017, 114, 3157–3162. [Google Scholar] [CrossRef] [Scilit]
- Chen, Z.; Yang, D.; Peng, X.; Lin, J.; Suc, Z.; Lia, J.; Zhang, X.; Weng, Y. Beneficial effect of atorvastatin-modified dendritic cells pulsed with myelin oligodendrocyte glycoprotein autoantigen on experimental autoimmune encephalomyelitis. Neuroreport 2018, 29, 317–327. [Google Scholar] [CrossRef] [Scilit]
- Wang, X.; Zhang, J.; Baylink, D.J.; Li1, C.-H.; Watts, D.M.; Xu, Y.; Qin, X.; Walter, M.H.; Tang, X. Targeting non-classical myelin epitopes to treat experimental autoimmune encephalomyelitis. Sci. Rep. 2016, 6, 36064. [Google Scholar] [CrossRef] [Scilit]
- Kalantari, T.; Karimi, M.H.; Ciric, B.; Yan, Y.; Rostami, A.; Kamali-Sarvestani, E. Tolerogenic dendritic cells produced by lentiviral-mediated CD40- and interleukin-23p19-specific shRNA can ameliorate experimental autoimmune encephalomyelitis by suppressing T helper type 17 cells. Clin. Exp. Immunol. 2014, 176, 180–189. [Google Scholar] [CrossRef] [Scilit]
- Mansilla, M.J.; Sellès-Moreno, C.; Fàbregas-Puig, S.; Amoedo, J.; Navarro-Barriuso, J.; Teniente-Serra, A.; Grau-López, L.; Ramo-Tello, C.; Martínez-Cáceres, E.M. Beneficial effect of tolerogenic dendritic cells pulsed with MOG autoantigen in experimental autoimmune encephalomyelitis. CNS Neurosci. Ther. 2015, 21, 222–230. [Google Scholar] [CrossRef] [Scilit]
- Mansilla, M.J.; Contreras-Cardone, R.; Navarro-Barriuso, J.; Cools, N.; Berneman, Z.; Ramo-Tello, C.; Martínez-Cáceres, E.M. Cryopreserved vitamin D3-tolerogenic dendritic cells pulsed with autoantigens as a potential therapy for multiple sclerosis patients. J. Neuroinflamm. 2016, 13, 113. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, Y.; Leng, X.; Luo, S.; Su, Z.; Luo, X.; Guo, H.; Mo, C.; Zou, Q.; Liu, Y.; Wang, Y. Tolerogenic dendritic cells generated with tofacitinib ameliorate experimental autoimmune encephalomyelitis through modulation of Th17/Treg balance. J. Immunol. Res. 2016, 2016, 5021537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xie, Z.; Chen, J.; Zheng, C.; Wu, J.; Cheng, Y.; Zhu, S.; Lin, C.; Cao, Q.; Zhu, J.; Jin, T. 1,25-dihydroxyvitamin D3-induced dendritic cells suppress experimental autoimmune encephalomyelitis by increasing proportions of the regulatory lymphocytes and reducing T helper type 1 and type 17 cells. Immunology 2017, 152, 414–424. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Papenfuss, T.L.; Powell, N.D.; McClain, M.A.; Bedarf, A.; Singh, A.; Gienapp, I.E.; Shawler, T.; Whitacre, C.C. Estriol generates tolerogenic dendritic cells in vivo that protect against autoimmunity. J. Immunol. 2011, 15, 186–3346. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Menges, M.; Rößner, S.; Voigtländer, C.; Schindler, H.; Kukutsch, N.A.; Bogdan, C.; Erb, K.; Schuler, G.; Lutz, M.B. Repetitive injections of dendritic cells matured with tumor necrosis factor α induce antigen-specific protection of mice from autoimmunity. J. Exp. Med. 2002, 195, 15–21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xiao, B.-G.; Huang, Y.-M.; Yang, J.-S.; Xu, L.-Y.; Link, H. Bone marrow-derived dendritic cells from experimental allergic encephalomyelitis induce immune tolerance to EAE in Lewis rats. Clin. Exp. Immunol. 2001, 125, 300–309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, Y.C.; Zhang, A.-H.; Yoon, J.; Culp, W.E.; Leesa, J.R.; Wucherpfennig, K.W.; Scott, D.W. Engineered MBP-specific human Tregs ameliorate MOG-induced EAE through IL-2-triggered inhibition of effector T cells. J. Autoimmun. 2018, 92, 77–86. [Google Scholar] [CrossRef] [Scilit]
- Pereira, B.d.; Fraefel, C.; Hilbe, M.; Ackermann, M.; Dresch, C. Transcriptional targeting of DCs with lentiviral vectors induces antigen-specific tolerance in a mouse model of multiple sclerosis. Gene Ther. 2013, 20, 556–566. [Google Scholar] [CrossRef] [Scilit]
- Eixarch, H.; Espejo, C.; Gómez, A.; Mansilla, M.J.; Castillo, M.; Mildner, A.; Vidal, F.; Gimeno, R.; Prinz, M.; Montalban, X.; et al. Tolerance induction in experimental autoimmune encephalomyelitis using non-myeloablative hematopoietic gene therapy with autoantigen. Mol. Ther. 2009, 17, 897–905. [Google Scholar] [CrossRef] [Scilit]
- Casacuberta-Serra, S.; Costa, C.; Eixarch, H.; Mansilla, M.J.; López-Estévez, S.; Martorell, L.; Parés, M.; Montalban, X.; Espejo, C.; Barquinero, J. Myeloid-derived suppressor cells expressing a self-antigen ameliorate experimental autoimmune encephalomyelitis. Exp. Neurol. 2016, 286, 50–60. [Google Scholar] [CrossRef] [Scilit]
- Tabansky, I.; Messina, M.D.; Bangeranye, C.; Goldstein, J.; Blitz-Shabbir, K.M.; Machado, S.; Jeganathan, V.; Wright, P.; Najjar, S.; Cao, Y.; et al. Advancing drug delivery systems for the treatment of multiple sclerosis. Immunol. Res. 2015, 63, 58–69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ballerini, C.; Baldi, G.; Aldinucci, A.; Maggi, P. Nanomaterial applications in multiple sclerosis inflamed Brain. J. Neuroimmune Pharmacol. 2015, 10, 1–13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gharagozloo, M.; Majewski, S.; Foldvari, M. Therapeutic applications of nanomedicine in autoimmune diseases: From immunosuppression to tolerance induction. Nanomed. Nanotechnol. 2015, 11, 1003–1018. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pires, L.R.; Marques, F.; Sousa, J.C.; Cerqueira, J.; Pinto, I.M. Nano- and micro-based systems for immunotolerance induction in multiple sclerosis. Hum. Vaccines Immunother. 2016, 12, 1886–1890. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Veld, R.H.I.; da Silva, C.G.; Kaijzel, E.L.; Chan, A.B.; Cruz, L.J. The Potential of nano-vehicle mediated therapy in vasculitis and multiple sclerosis. Curr. Pharm. Des. 2017, 23, 1985–1992. [Google Scholar] [CrossRef] [Scilit]
- Gammon, J.M.; Jewell, C.M. Engineering immune tolerance with biomaterials. Adv. Healthc. Mater. 2019, 8, e1801419. [Google Scholar] [CrossRef] [Scilit]
- Pei, W.; Wan, X.; Shahzad, K.A.; Zhang, L.; Song, S.; Jin, X.; Wang, L.; Zhao, C.; Shen, C. Direct modulation of myelin-autoreactive CD4+ and CD8+ T cells in EAE mice by a tolerogenic nanoparticle co-carrying myelin peptide-loaded major histocompatibility complexes, CD47 and multiple regulatory molecules. Int. J. Nanomed. 2018, 13, 3731–3750. [Google Scholar] [CrossRef] [Scilit]
- Sestak, J.O.; Sullivan, B.P.; Thati, S.; Northrup, L.; Hartwell, B.; Antunez, L.; Forrest, M.L.; Vines, C.M.; Siahaan, T.J.; Berkland, C. Codelivery of antigen and an immune cell adhesion inhibitor is necessary for efficacy of soluble antigen arrays in experimental autoimmune encephalomyelitis. Mol. Ther. Methods Clin. Dev. 2014, 1, 14008. [Google Scholar] [CrossRef] [Scilit]
- Thati, S.; Kuehl, C.; Hartwell, B.; Sestak, J.; Siahaan, T.; Forrest, M.L.; Berkland, C. Routes of Administration and dose optimization of soluble antigen arrays in mice with experimental autoimmune encephalomyelitis. J. Pharm. Sci. 2015, 104, 714–721. [Google Scholar] [CrossRef] [Scilit]
- Hartwell, B.L.; Pickens, C.J.; Leon, M.; Berkland, C. Multivalent antigen arrays exhibit high avidity binding and modulation of B cell receptor-mediated signaling to drive efficacy against experimental autoimmune encephalomyelitis. Biomacromolecules 2017, 18, 1893–1907. [Google Scholar] [CrossRef] [Scilit]
- Hartwell, B.L.; Pickens, C.J.; Leon, M.; Northrup, L.; Christopher, M.; Griffin, J.D.; Martinez-Becerra, F.; Berkland, C. Soluble antigen arrays disarm antigen-specific B cells to promote lasting immune tolerance in experimental autoimmune encephalomyelitis. J. Autoimmun. 2018, 93, 76–88. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tostanoski, L.H.; Chiu, Y.-C.; Andorko, J.I.; Guo, M.; Zeng, X.; Zhang, P.; Royal, W., III; Jewell, C.M. Design of polyelectrolyte multilayers to promote immunological tolerance. ACS Nano 2016, 10, 9334–9345. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hess, K.L.; Andorko, J.I.; Tostanoski, L.H.; Jewell, C.M. Polyplexes assembled from self-peptides and regulatory nucleic acids blunt toll-like receptor signaling to combat autoimmunity. Biomaterials 2017, 118, 51–62. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tseveleki, V.; Tselios, T.; Kanistras, I.; Koutsoni, O.; Karamita, M.; Vamvakas, S.-S.; Apostolopoulos, V.; Dotsika, E.; Matsoukas, J.; Lassmann, H.; et al. Mannan-conjugated myelin peptides prime non-pathogenic Th1 and Th17 cells and ameliorate experimental autoimmune encephalomyelitis. Exp. Neurol. 2015, 267, 254–267. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Belogurov, A.A., Jr.; Stepanov, A.V.; Smirnov, I.V.; Melamed, D.; Bacon, A.; Mamedov, A.E.; Boitsov, V.M.; Sashchenko, L.P.; Ponomarenko, N.A.; Sharanova, S.N.; et al. Liposome-encapsulated peptides protect against experimental allergic encephalitis. FASEB J. 2013, 27, 222–231. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pujol-Autonell, I.; Mansilla, M.-J.; Rodriguez-Fernandez, S.; Cano-Sarabia, M.; Navarro-Barriuso1, J.; Ampudia, R.-M.; Rius, A.; Garcia-Jimeno, S.; Perna-Barrull, D.; Martinez-Caceres, E.; et al. Liposome-based immunotherapy against autoimmune diseases: Therapeutic effect on multiple sclerosis. Nanomedicine 2017, 12, 1231–1242. [Google Scholar] [CrossRef] [Scilit]
- Belogurov, A.; Zakharov, K.; Lomakin, Y.; Surkov, K.; Avtushenko, S.; Kruglyakov, P.; Smirnov, I.; Makshakov, G.; Lockshin, C.; Gregoriadis, G.; et al. CD206-targeted liposomal myelin basic protein peptides in patients with multiple sclerosis resistant to first-line disease-modifying therapies: A first-in-human, proof-of-concept dose-escalation study. Neurotherapeutics 2016, 13, 895–904. [Google Scholar] [CrossRef] [Scilit]
- Lomakin, Y.; Belogurov, A., Jr.; Glagoleva, I.; Stepanov, A.; Zakharov, K.; Okunola, J.; Smirnov, I.; Genkin, D.; Gabibov, A. Administration of myelin basic protein peptides encapsulated in mannosylated liposomes normalizes level of serum TNF-α and IL-2 and chemoattractants CCL2 and CCL4 in multiple sclerosis patients. Mediat. Inflamm. 2016, 2016, 2847232. [Google Scholar] [CrossRef] [Scilit]
- Cappellano, G.; Woldetsadik, A.D.; Orilieri, E.; Shivakumar, Y.; Rizzi, M.; Carniato, F.; Gigliotti, C.L.; Boggio, E.; Clemente, N.; Comi, C.; et al. Subcutaneous inverse vaccination with PLGA particles loaded with aMOG peptide and IL-10 decreases the severity of experimental autoimmune encephalomyelitis. Vaccine 2014, 32, 5681–5689. [Google Scholar] [CrossRef] [Scilit]
- Casey, L.M.; Pearson, R.M.; Hughes, K.R.; Liu, J.M.H.; Rose, J.A.; North, M.G.; Wang, L.Z.; Lei, M.; Miller, S.D.; Shea, L.D. Conjugation of transforming growth factor Beta to antigen-loaded Poly(lactide-co-glycolide) nanoparticles enhances efficiency of antigen-specific tolerance. Bioconjug. Chem. 2018, 29, 813–823. [Google Scholar] [CrossRef] [Scilit]
- Cho, J.J.; Stewart, J.M.; Drashansky, T.T.; Brusko, M.A.; Zuniga, A.N.; Lorentsen, K.J.; Keselowsky, B.G.; Avram, D. An antigen-specific semi-therapeutic treatment with local delivery of tolerogenic factors through a dual-sized microparticle system blocks experimental autoimmune encephalomyelitis. Biomaterials 2017, 143, 79–92. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gholamzad, M.; Ebtekar, M.; Ardestani, M.S. Intravenous injection of myelin oligodendrocyte glycoprotein-coated PLGA microparticles have tolerogenic effects in experimental autoimmune encephalomyelitis. Iran J. Allergy Asthma Immunol. 2017, 16, 27–281. [Google Scholar]
- Hunter, Z.; McCarthy, D.P.; Yap, W.T.; Harp, C.T.; Getts, D.R.; Shea, L.D.; Miller, S.D. A biodegradable nanoparticle platform for the induction of antigen-specific immune tolerance for treatment of autoimmune disease. ACS Nano 2014, 8, 2148–2160. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maldonado, R.A.; LaMothe, R.A.; Ferrari, J.D.; Zhang, A.-H.; Rossi, R.J.; Kolte, P.N.; Griset, A.P.; O’Neil, C.; Altreuter, D.H.; Browning, E.; et al. Polymeric synthetic nanoparticles for the induction of antigen-specific immunological tolerance. Proc. Natl. Acad. Sci. USA 2014, 112, E156–E165. [Google Scholar] [CrossRef] [Scilit]
- McCarthy, D.P.; Yap, J.W.-T.; Harp, C.T.; Song, W.K.; Chen, J.; Pearson, R.M.; Miller, S.D.; Shea, L.D. An antigen-encapsulating nanoparticle platform for TH1/17 immune tolerance therapy. Nanomedicine 2017, 13, 191–200. [Google Scholar] [CrossRef] [Scilit]
- Saito, E.; Kuo, R.; Kramer, K.R.; Gohel, N.; Giles, D.A.; Moore, B.B.; Miller, S.D.; Shea, L.D. Design of biodegradable nanoparticles to modulate phenotypes of antigen presenting cells for antigen-specific treatment of autoimmune disease. Biomaterials 2019, 222, 119432. [Google Scholar] [CrossRef] [Scilit]
- Wan, X.; Pei, W.; Shahzad, K.A.; Zhang, L.; Song, S.; Jin, X.; Wang, L.; Zhao, C.; Shen, C. A Tolerogenic artificial APC durably ameliorates experimental autoimmune encephalomyelitis by directly and selectively modulating myelin peptide–autoreactive CD4+ and CD8+ T cell. J. Immunol. 2018, 201, 1194–1210. [Google Scholar] [CrossRef] [Scilit]
- Zhao, H.; Kiptoo, P.; Williams, T.D.; Siahaan, T.J.; Topp, E.M. Immune response to controlled release of immunomodulating peptides in a murine experimental autoimmune encephalomyelitis (EAE) model. J. Control. Release 2010, 141, 145–152. [Google Scholar] [CrossRef] [Scilit]
- Pearson, R.M.; Casey, L.M.; Hughes, K.R.; Wang, L.Z.; North, M.G.; Getts, D.R.; Miller, S.D.; Shea, L.D. Controlled delivery of single or multiple antigens in tolerogenic nanoparticles using peptide-polymer bioconjugates. Mol. Ther. 2017, 25, 1655–1664. [Google Scholar] [CrossRef] [Scilit]
- Sestak, J.O.; Fakhari, A.; Badawi, A.H.; Siahaan, T.J.; Berkland, C. Structure, size, and solubility of antigen arrays determines efficacy in experimental autoimmune encephalomyelitis. AAPS J. 2014, 16, 1185–1193. [Google Scholar] [CrossRef] [Scilit]
- Kuo, R.; Saito, E.; Miller, S.D.; Shea, L.D. Peptide-conjugated nanoparticles reduce positive co-stimulatory expression and T cell activity to induce tolerance. Mol. Ther. 2017, 25, 1676–1685. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Getts, D.R.; Martin, A.J.; McCarthy, D.P.; Terry, R.L.; Hunter, Z.N.; Yap, W.T.; Getts, M.T.; Pleiss, M.; Luo, X.; King, N.J.C.; et al. Microparticles bearing encephalitogenic peptides induce T-cell tolerance and ameliorate experimental autoimmune encephalomyelitis. Nat. Biotechnol. 2012, 30, 1217–1224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tostanoski, L.H.; Chiu, Y.-C.; Gammon, J.M.; Simon, T.; Andorko, J.I.; Bromberg, J.S.; Jewell, C.M. Reprogramming the local lymph node microenvironment promotes tolerance that is systemic and antigen-specific. Cell Rep. 2016, 16, 2940–2952. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Büyüktimkin, B.; Wang, Q.; Kiptoo, P.; Stewart, J.M.; Berkland, C.; Siahaan, T.J. Vaccine-like controlled-release delivery of an immunomodulating peptide to treat experimental autoimmune encephalomyelitis. Mol. Pharm. 2012, 9, 979–985. [Google Scholar] [CrossRef] [Scilit]
- Northrup, L.; Sestak, J.O.; Sullivan, B.P.; Thati, S.; Hartwell, B.L.; Siahaan, T.J.; Vines, C.M.; Berkland, C. Co-delivery of autoantigen and B7 pathway modulators suppresses experimental autoimmune encephalomyelitis. AAPS J. 2014, 16, 1204–1213. [Google Scholar] [CrossRef] [Scilit]
- Kuehl, C.; Thati, S.; Sullivan, B.; Sestak, J.; Thompson, M.; Siahaan, T.; Berkland, C. Pulmonary administration of soluble antigen arrays is superior to antigen in treatment of experimental autoimmune encephalomyelitis. J. Pharm. Sci. 2017, 106, 3293–3302. [Google Scholar] [CrossRef] [Scilit]
- Hess, K.L.; Oh, E.; Tostanoski, L.H.; Andorko, J.I.; Susumu, K.; Deschamps, J.R.; Medintz, I.L.; Jewell, C.M. Engineering immunological tolerance using quantum dots to tune the density of self-antigen display. Adv. Funct. Mater. 2017, 27. [Google Scholar] [CrossRef] [Scilit]
- Clemente-Casares, X.; Blanco, J.; Ambalavanan, P.; Yamanouchi, J.; Singha, S.; Fandos, C.; Tsai, S.; Wang, J.; Garabatos, N.; Izquierdo, C.; et al. Expanding antigen-specific regulatory networks to treat autoimmunity. Nature 2016, 530, 434–440. [Google Scholar] [CrossRef] [Scilit]
- Yeste, A.; Nadeau, M.; Burns, E.J.; Weiner, H.L.; Qu, F.J. Nanoparticle-mediated codelivery of myelin antigen and a tolerogenic small molecule suppresses experimental autoimmune encephalomyelitis. Proc. Natl. Acad. Sci. USA 2012, 109, 11270–11275. [Google Scholar] [CrossRef] [Scilit]
- Katsara, M.; Deraos, G.; Tselios, T.; Matsoukas, J.; Apostolopoulos, V. Design of novel cyclic altered peptide ligands of myelin basic protein MBP83–99 that modulate immune responses in SJL/J mice. J. Med. Chem. 2008, 51, 3971–3978. [Google Scholar] [CrossRef] [Scilit]
- Yu, L.; Yang, F.; Jiang, L.; Chen, Y.; Wang, K.; Xu, F.; Wei, Y.; Cao, X.; Wang, J.; Cai, Z. Exosomes with membrane-associated TGF-β1 from gene-modified dendritic cells inhibit murine EAE independently of MHC restriction. Eur. J. Immunol. 2013, 43, 2461–2472. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buerth, C.; Mausberg, A.K.; Heininger, M.K.; Hartung, H.-P.; Kieseier, B.C.; Ernst, J.F. Oral tolerance induction in experimental autoimmune encephalomyelitis with Candida utilis expressing the immunogenic MOG35-55 peptide. PLoS ONE 2016, 11, e0155082. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kappos, L.; Comi, G.; Panitch, H.; Oger, J.; Antel, J.; Conlon, P.; Steinman, L. The Altered peptide ligand in relapsing MS study group, Induction of a non-encephalitogenic type 2 T helper-cell autoimmune response in multiple sclerosis after administration of an altered peptide ligand in a placebo-controlled, randomized phase II trial. Nat. Med. 2000, 6, 1176–1182. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Goodkin, D.E.; Shulman, M.; Winkelhake, J.; Waubant, E.; Andersson, P.; Stewart, T.; Nelson, S.; Fischbein, N.; Coyle, P.K.; Frohman, E.; et al. A phase I trial of solubilized DR2:MBP84-102 (AG284) in multiple sclerosis. Neurology 2000, 54, 1414–1420. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Warren, K.G.; Catz, I.; Ferenczi, L.Z.; Krantz, M.J. Intravenous synthetic peptide MBP8298 delayed disease progression in an HLA Class II-defined cohort of patients with progressive multiple sclerosis: Results of a 24-month double-blind placebo-controlled clinical trial and 5 years of follow-up treatment. Eur. J. Neurol. 2006, 13, 887–895. [Google Scholar] [CrossRef] [Scilit]
- Freedman, M.S.; Bar-Or, A.; Oger, J.; Traboulsee, A.; Patry, D.; Young, C.; Olsson, T.; Li, D.; Hartung, H.-P.; Krantz, M.; et al. A phase III study evaluating the efficacy and safety of MBP8298 in secondary progressive MS. Neurology 2011, 77, 1551–1560. [Google Scholar] [CrossRef] [Scilit]
- Offner, H.; Burrows, G.G.; Ferro, A.J.; Vandenbark, A.A. RTL therapy for multiple sclerosis: A Phase I clinical study. J. Neuroimmunol. 2011, 231, 7–14. [Google Scholar] [CrossRef] [Scilit]
- Yadav, V.; Bourdette, D.N.; Bowen, J.D.; Lynch, S.G.; Mattson, D.; Preiningerova, J.; Bever, C.T.; Simon, J.; Goldstein, A.; Burrows, G.G.; et al. Recombinant T-cell receptor ligand (RTL) for treatment of multiple sclerosis: A double-blind, placebo-controlled, Phase 1, dose-escalation study. Autoimmune Dis. 2012, 2012, 954739. [Google Scholar] [CrossRef] [Scilit]
- Loo, E.W.; Krantz, M.J.; Agrawal, B. High dose antigen treatment with a peptide epitope of myelin basic protein modulates T cells in multiple sclerosis patients. Cell. Immunol. 2012, 280, 10–15. [Google Scholar] [CrossRef] [Scilit]
- Lutterotti, A.; Yousef, S.; Sputtek, A.; Stürner, K.H.; Stellmann, J.-P.; Breiden, P.; Reinhardt, S.; Schulze, C.; Bester, M.; Heesen, C.; et al. Antigen-specific tolerance by autologous myelin peptide–coupled cells: A Phase 1 trial in multiple sclerosis. Sci. Transl. Med. 2013, 5, 188ra75. [Google Scholar] [CrossRef] [Scilit]
- Bar-Or, A.; Vollmer, T.; Antel, J.; Arnold, D.L.; Bodner, C.A.; Campagnolo, D.; Gianettoni, J.; Jalili, F.; Kachuck, N.; Lapierre, Y.; et al. Induction of antigen-specific tolerance in multiple sclerosis after immunization with a DNA encoding myelin basic protein in a randomized, placebo-controlled Phase I/II trial. Arch. Neurol. 2007, 64, 1407–1415. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Juryńczyk, M.; Walczak, A.; Jurewicz, A.; Jesionek-Kupnicka, D.; Szczepanik, M.; Selmaj, K. Immune regulation of multiple sclerosis by transdermally applied myelin peptides. Ann. Neurol. 2010, 68, 593–601. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Walczak, A.; Siger, M.; Ciach, A.; Szczepanik, M.; Selmaj, K. Transdermal application of myelin peptides in multiple sclerosis treatment. JAMA Neurol. 2013, 70, 1105–1109. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garren, H.; Robinson, W.H.; Krasulova´, E.; Havrdova´, E.; Nadj, C.; Selmaj, K.; Losy, J.; Nadj, I.; Radue, E.-W.; Kidd, B.A.; et al. Steinman, and the BHT-3009 Study Group, Phase 2 trial of a DNA vaccine encoding myelin basic protein for multiple sclerosis. Ann. Neurol. 2008, 63, 611–620. [Google Scholar] [CrossRef] [Scilit]
- Papadopoulou, A.; von Felten, S.; Traud, S.; Rahman, A.; Quan, J.; King, R.; Garren, H.; Steinman, L.; Cutter, G.; Kappos, L.; et al. Evolution of MS lesions to black holes under DNA vaccine treatment. J. Neurol. 2012, 259, 1375–1382. [Google Scholar] [CrossRef] [Scilit]
- Chataway, J.; Martin, K.; Barrell, K.; Sharrack, B.; Stolt, P.; Wraith, D.C. Effects of ATX-MS-1467 immunotherapy over 16 weeks in relapsing multiple sclerosis. Neurology 2018, 90, e955–e962. [Google Scholar] [CrossRef] [Scilit]
- Zubizarreta, I.; Flórez-Graub, G.; Vila, G.; Cabezón, R.; España, C.; Andorra, M.; Saiza, A.; Llufriu, S.; Sepulveda, M.; Sola-Valls, N.; et al. Immune tolerance in multiple sclerosis and neuromyelitis optica with peptide-loaded tolerogenic dendritic cells in a phase 1b trial. Proc. Natl. Acad. Sci. USA 2019, 116, 8463–8470. [Google Scholar] [CrossRef] [Scilit]
- Willekens, B.; Presas-Rodríguez, S.; Mansilla, M.J.; Derdelinckx, J.; Lee, W.-P.; Nijs, G.; de Laere, M.; Wens, I.; Cras, P.; Parizel, P.; et al. On behalf of the RESTORE consortium, Tolerogenic dendritic cell-based treatment for multiple sclerosis (MS): A harmonized study protocol for two phase I clinical trials comparing intradermal and intranodal cell administration. BMJ Open 2019, 9, e030309. [Google Scholar] [CrossRef] [Scilit]
- Seledtsova, G.V.; Ivanova, I.P.; Shishkov, A.A.; Seledtsov, V.I. Immune responses to polyclonal T-cell vaccination in patients with progressive multiple sclerosis. J. Immunotoxicol. 2016, 13, 879–884. [Google Scholar] [CrossRef] [Scilit]
- Loftus, B.; Newsom, B.; Montgomery, M.; von Gynz-Rekowski, K.; Riser, M.; Inman, S.; Garces, P.; Rill, D.; Zhang, J.; Williams, J.C. Autologous attenuated T-cell vaccine (Tovaxin®) dose escalation in multiple sclerosis relapsing–remitting and secondary progressive patients nonresponsive to approved immunomodulatory therapies. Clin. Immunol. 2009, 131, 202–215. [Google Scholar] [CrossRef] [Scilit]
- Fox, E.; Wynn, D.; Cohan, S.; Rill, D.; McGuire, D.; Markowitz, C. A randomized clinical trial of autologous T-cell therapy in multiple sclerosis: Subset analysis and implications for trial design. Mult. Scler. J. 2012, 18, 843–852. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karussis, D.; Shor, H.; Yachnin, J.; Lanxner, N.; Amiel, M.; Baruch, K.; Keren-Zur, Y.; Haviv, O.; Filippi, M.; Petrou, P.; et al. T Cell vaccination benefits relapsing progressive multiple sclerosis patients: A randomized, double-blind clinical trial. PLoS ONE 2012, 7, e50478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van der, A.A.; Hellings, N.; Medaer, R.; Gelin, G.; Palmers, Y.; Rauss, J.; Stinissen, P. T cell vaccination in multiple sclerosis patients with autologous CSF-derived activated T cells: Results from a pilot study. Clin. Exp. Immunol. 2003, 131, 155–168. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, J.Z.; Rivera, V.M.; Tejada-Simon, M.V.; Yang, D.; Hong, J.; Li, S.; Haykal, H.; Killian, J.; Zang, Y.C.Q. T cell vaccination in multiple sclerosis: Results of a preliminary study. J. Neurol. 2002, 249, 212–218. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Correale, J.; Lunda, B.; McMillan, M.; Koa, D.Y.; McCarthy, K.; Weiner, L.P. T cell vaccination in secondary progressive multiple sclerosis. J. Neuroimmunol. 2000, 107, 130–139. [Google Scholar] [CrossRef] [Scilit]
- Achiron, A.; Lavie, G.; Kishner, I.; Stern, Y.; Sarova-Pinhas, I.; Ben-Aharon, T.; Barak, Y.; Raz, H.; Lavie, M.; Barliya, T.; et al. T cell vaccination in multiple sclerosis relapsing–remitting nonresponders patients. Clin. Immunol. 2004, 113, 155–160. [Google Scholar] [CrossRef] [Scilit]
- Zang, Y.C.Q.; Hong, J.; Rivera, V.M.; Killian, J.; Zhang, J.Z. Preferential recognition of TCR hypervariable regions by human anti-idiotypic T cells induced by T cell vaccination. J. Immunol. 2000, 164, 4011–4017. [Google Scholar] [CrossRef] [Scilit]
- Vandenbark, A.A.; Culbertson, N.E.; Bartholomew, R.M.; Huan, J.; Agotsch, M.; LaTocha, D.; Yadav, V.; Mass, M.; Whitham, R.; Lovera, J.; et al. Therapeutic vaccination with a trivalent T-cell receptor (TCR) peptide vaccine restores deficient FoxP3 expression and TCR recognition in subjects with multiple sclerosis. Immunology 2007, 123, 66–78. [Google Scholar] [CrossRef] [Scilit]
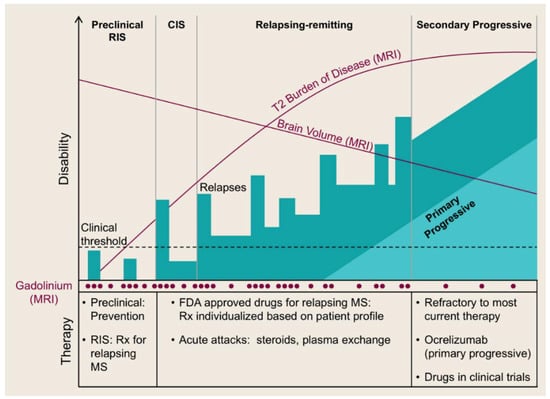
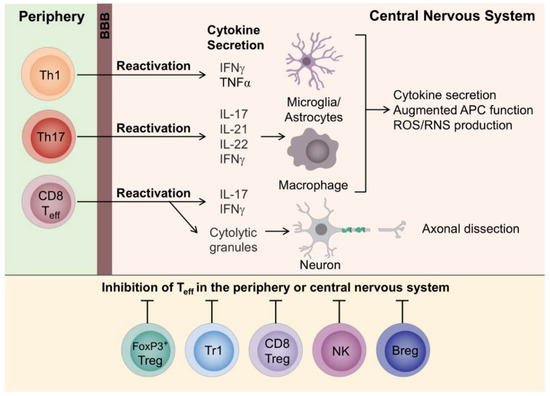
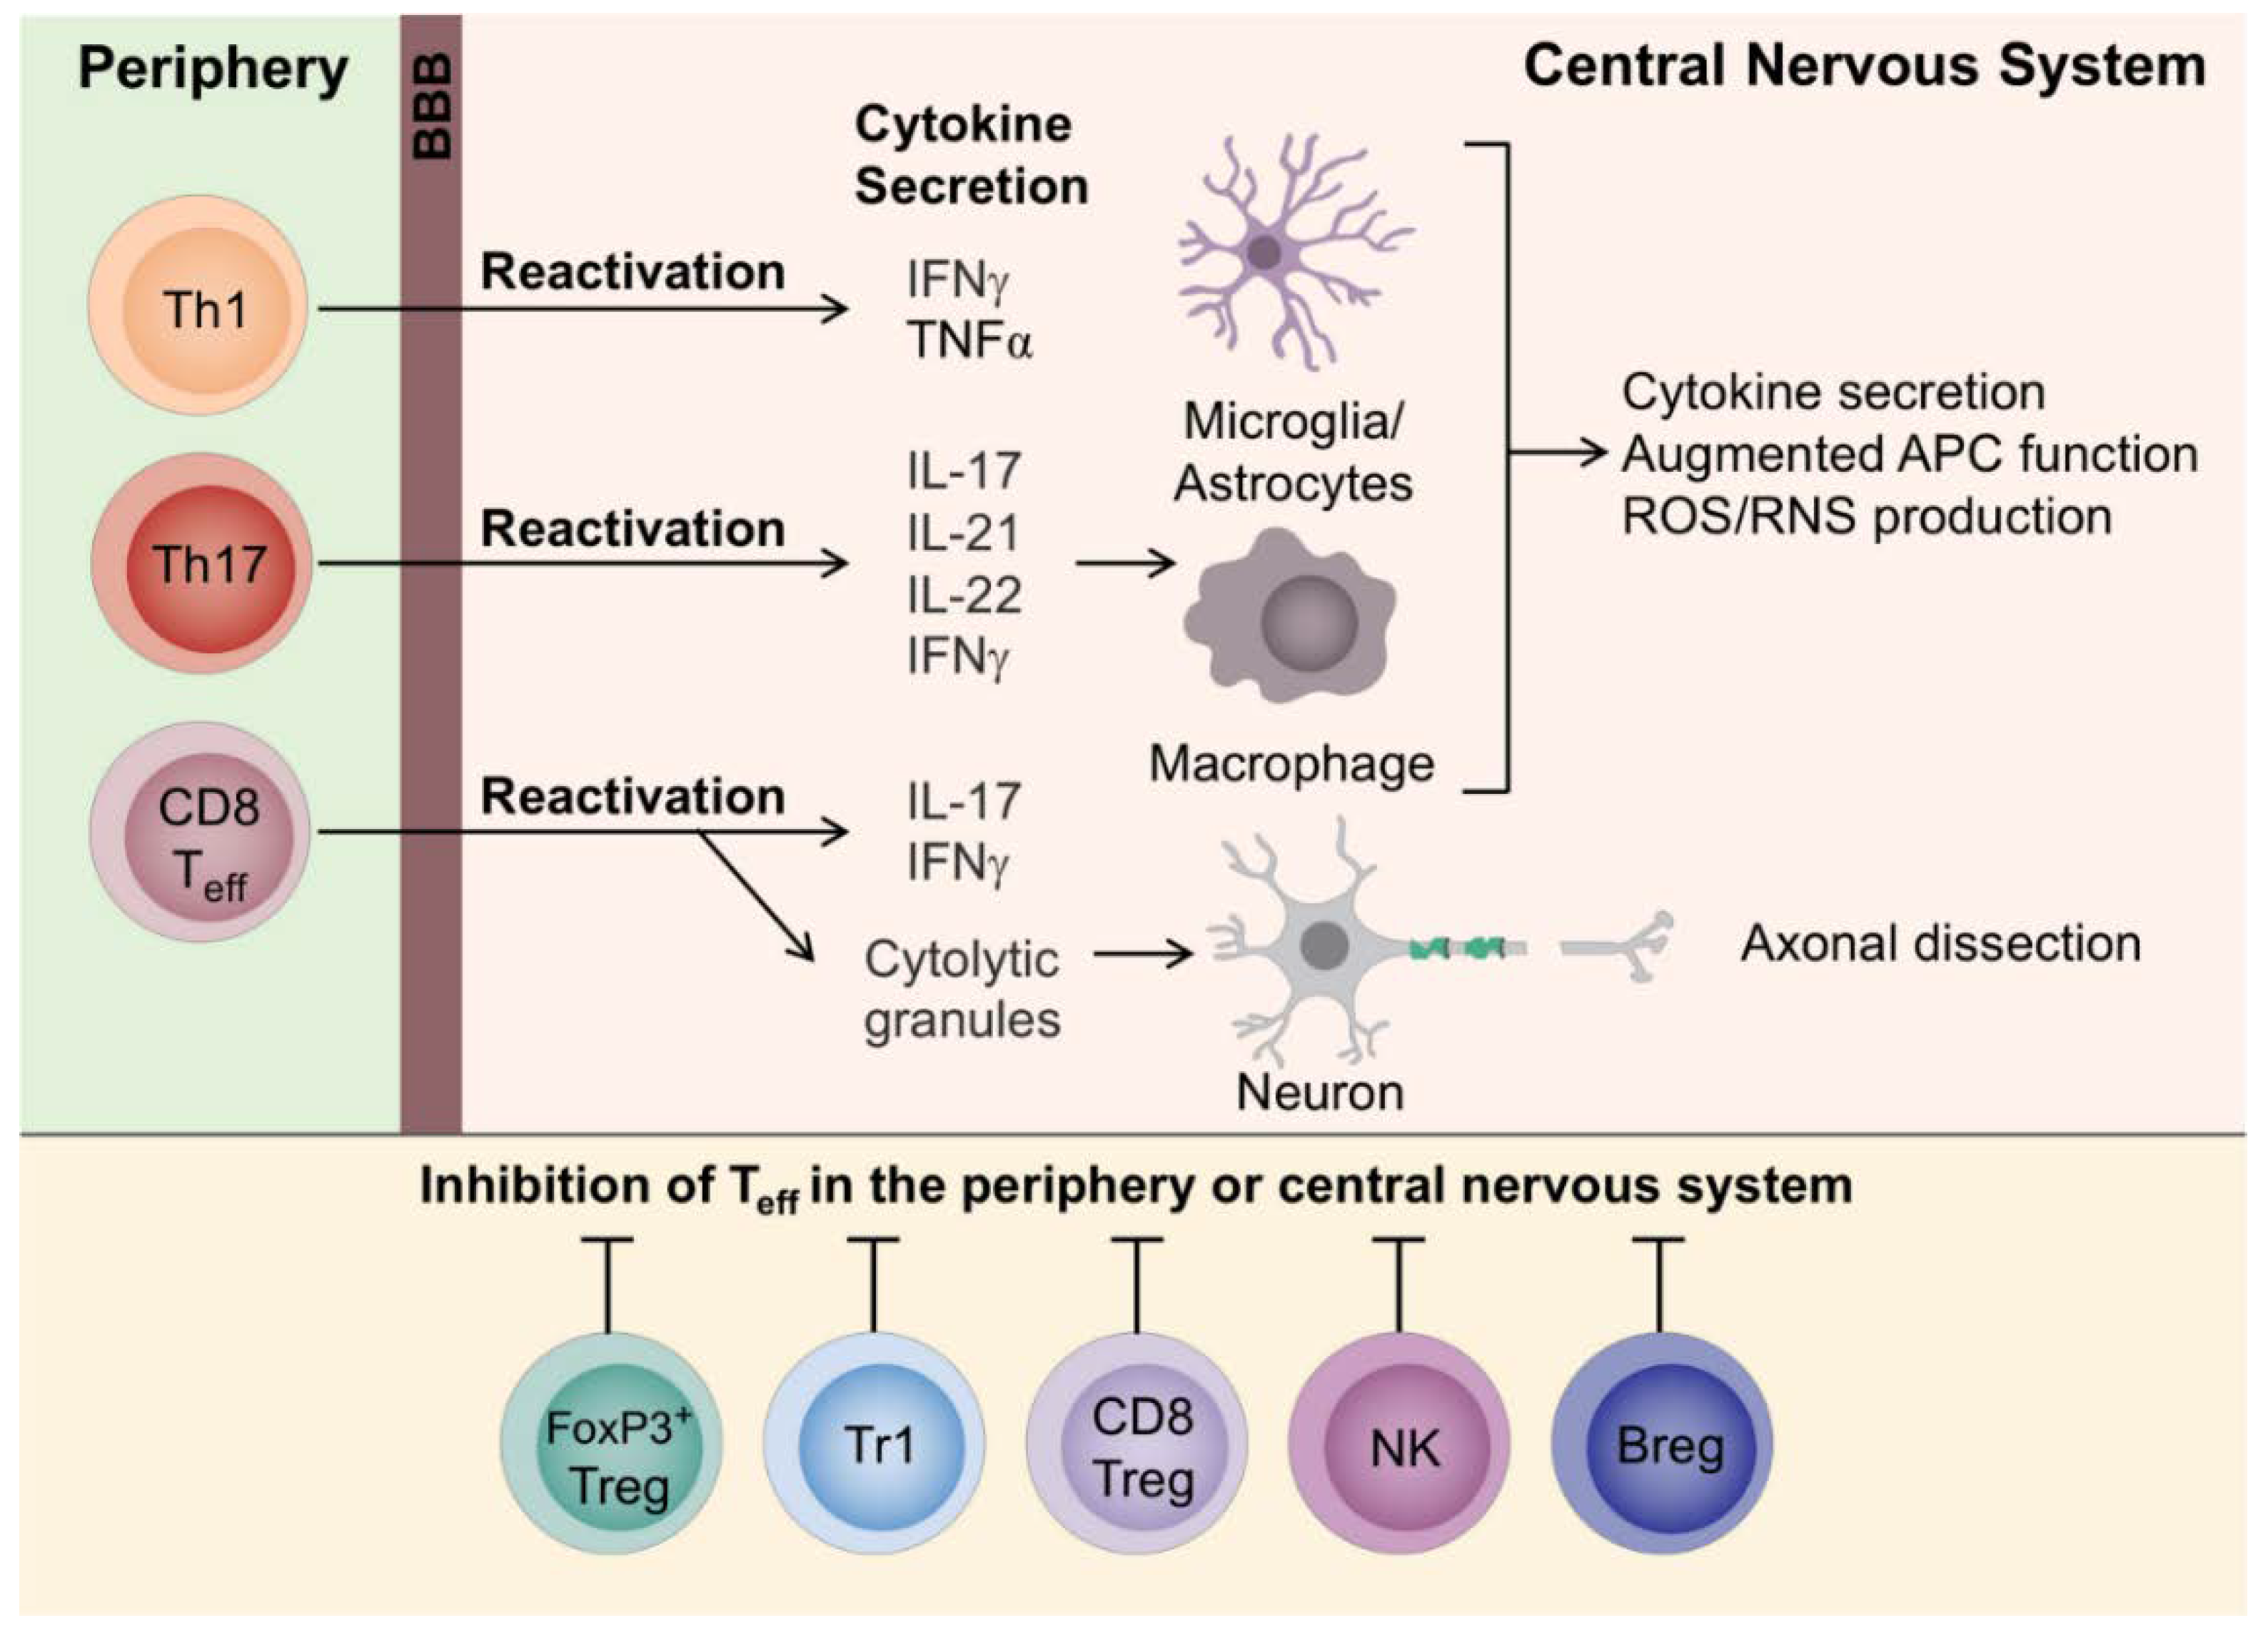
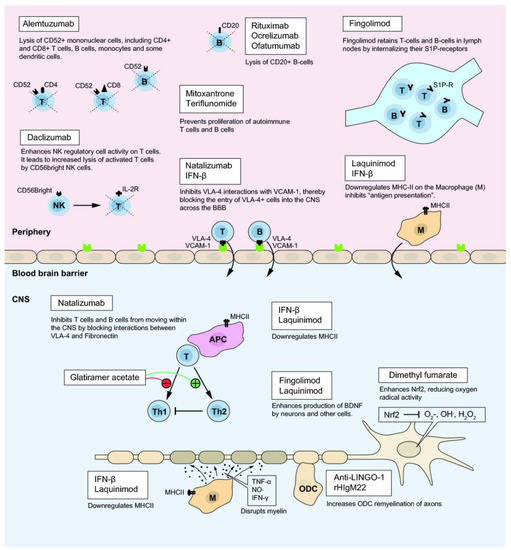
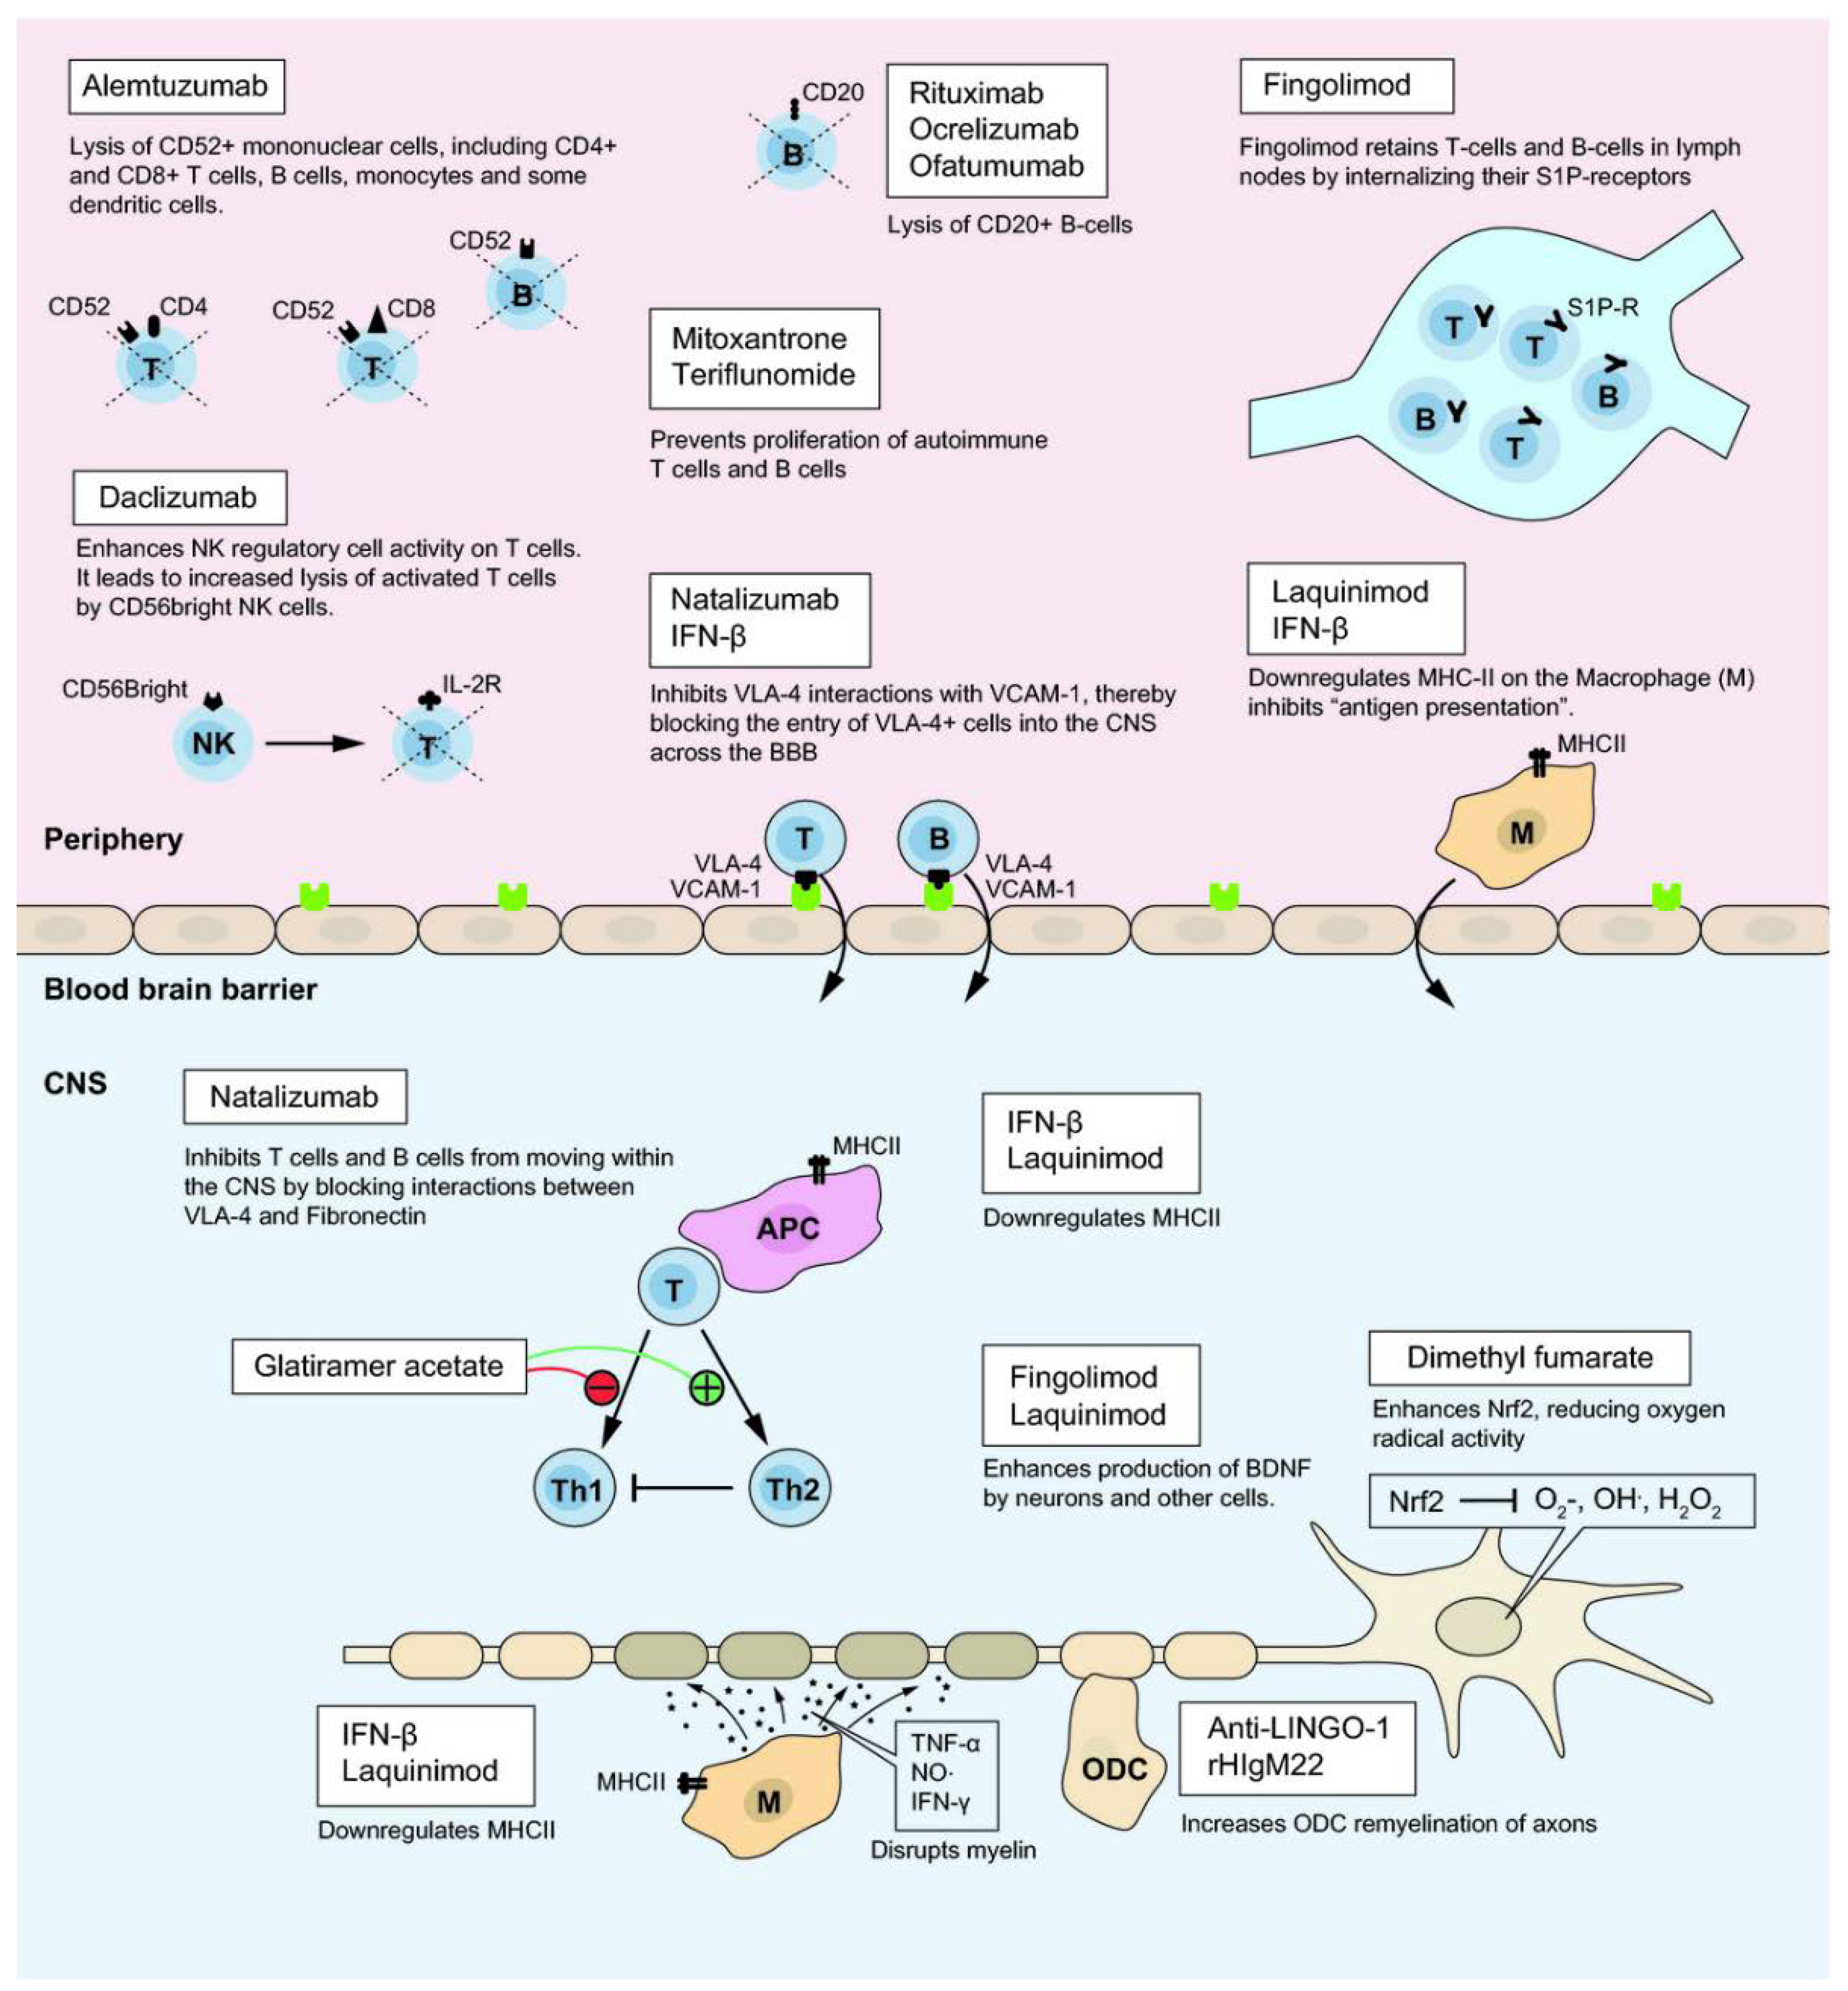
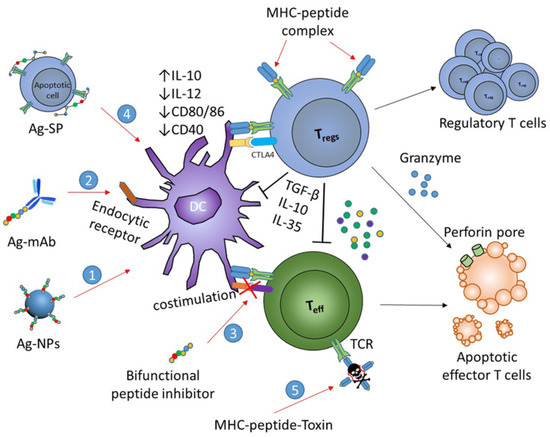
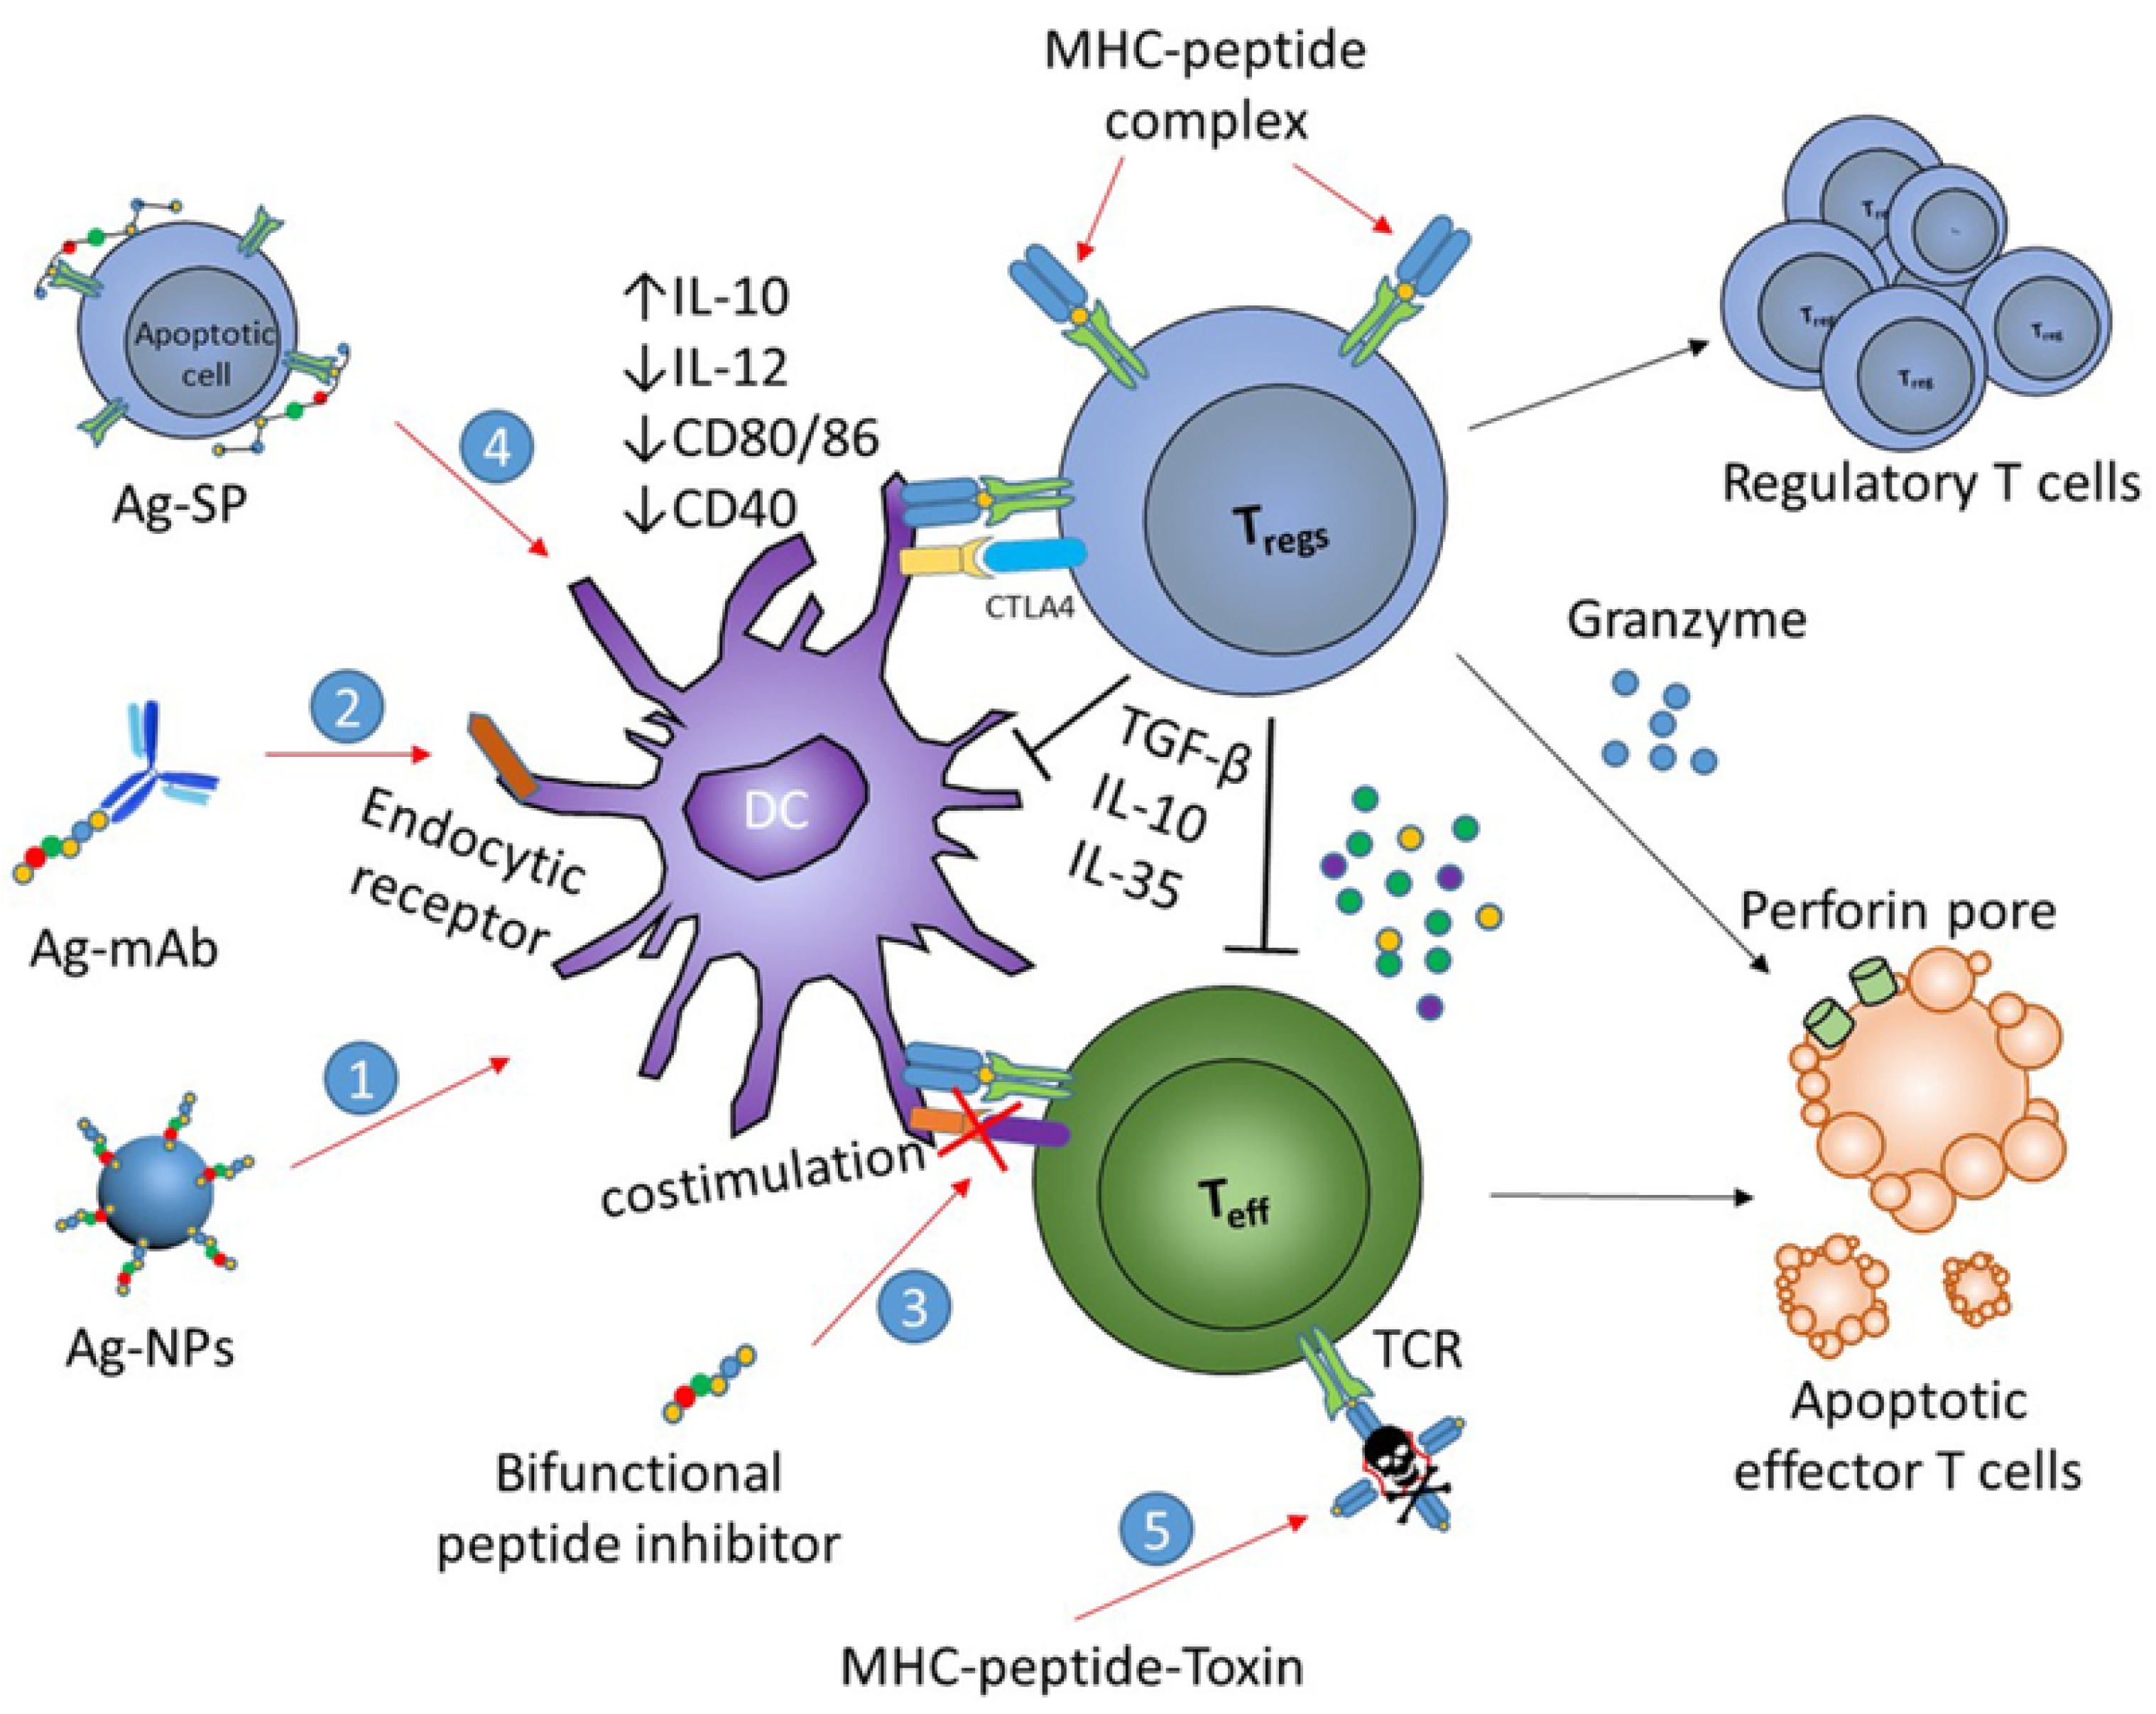
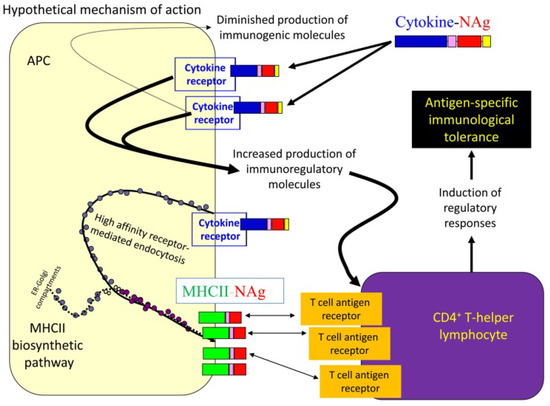
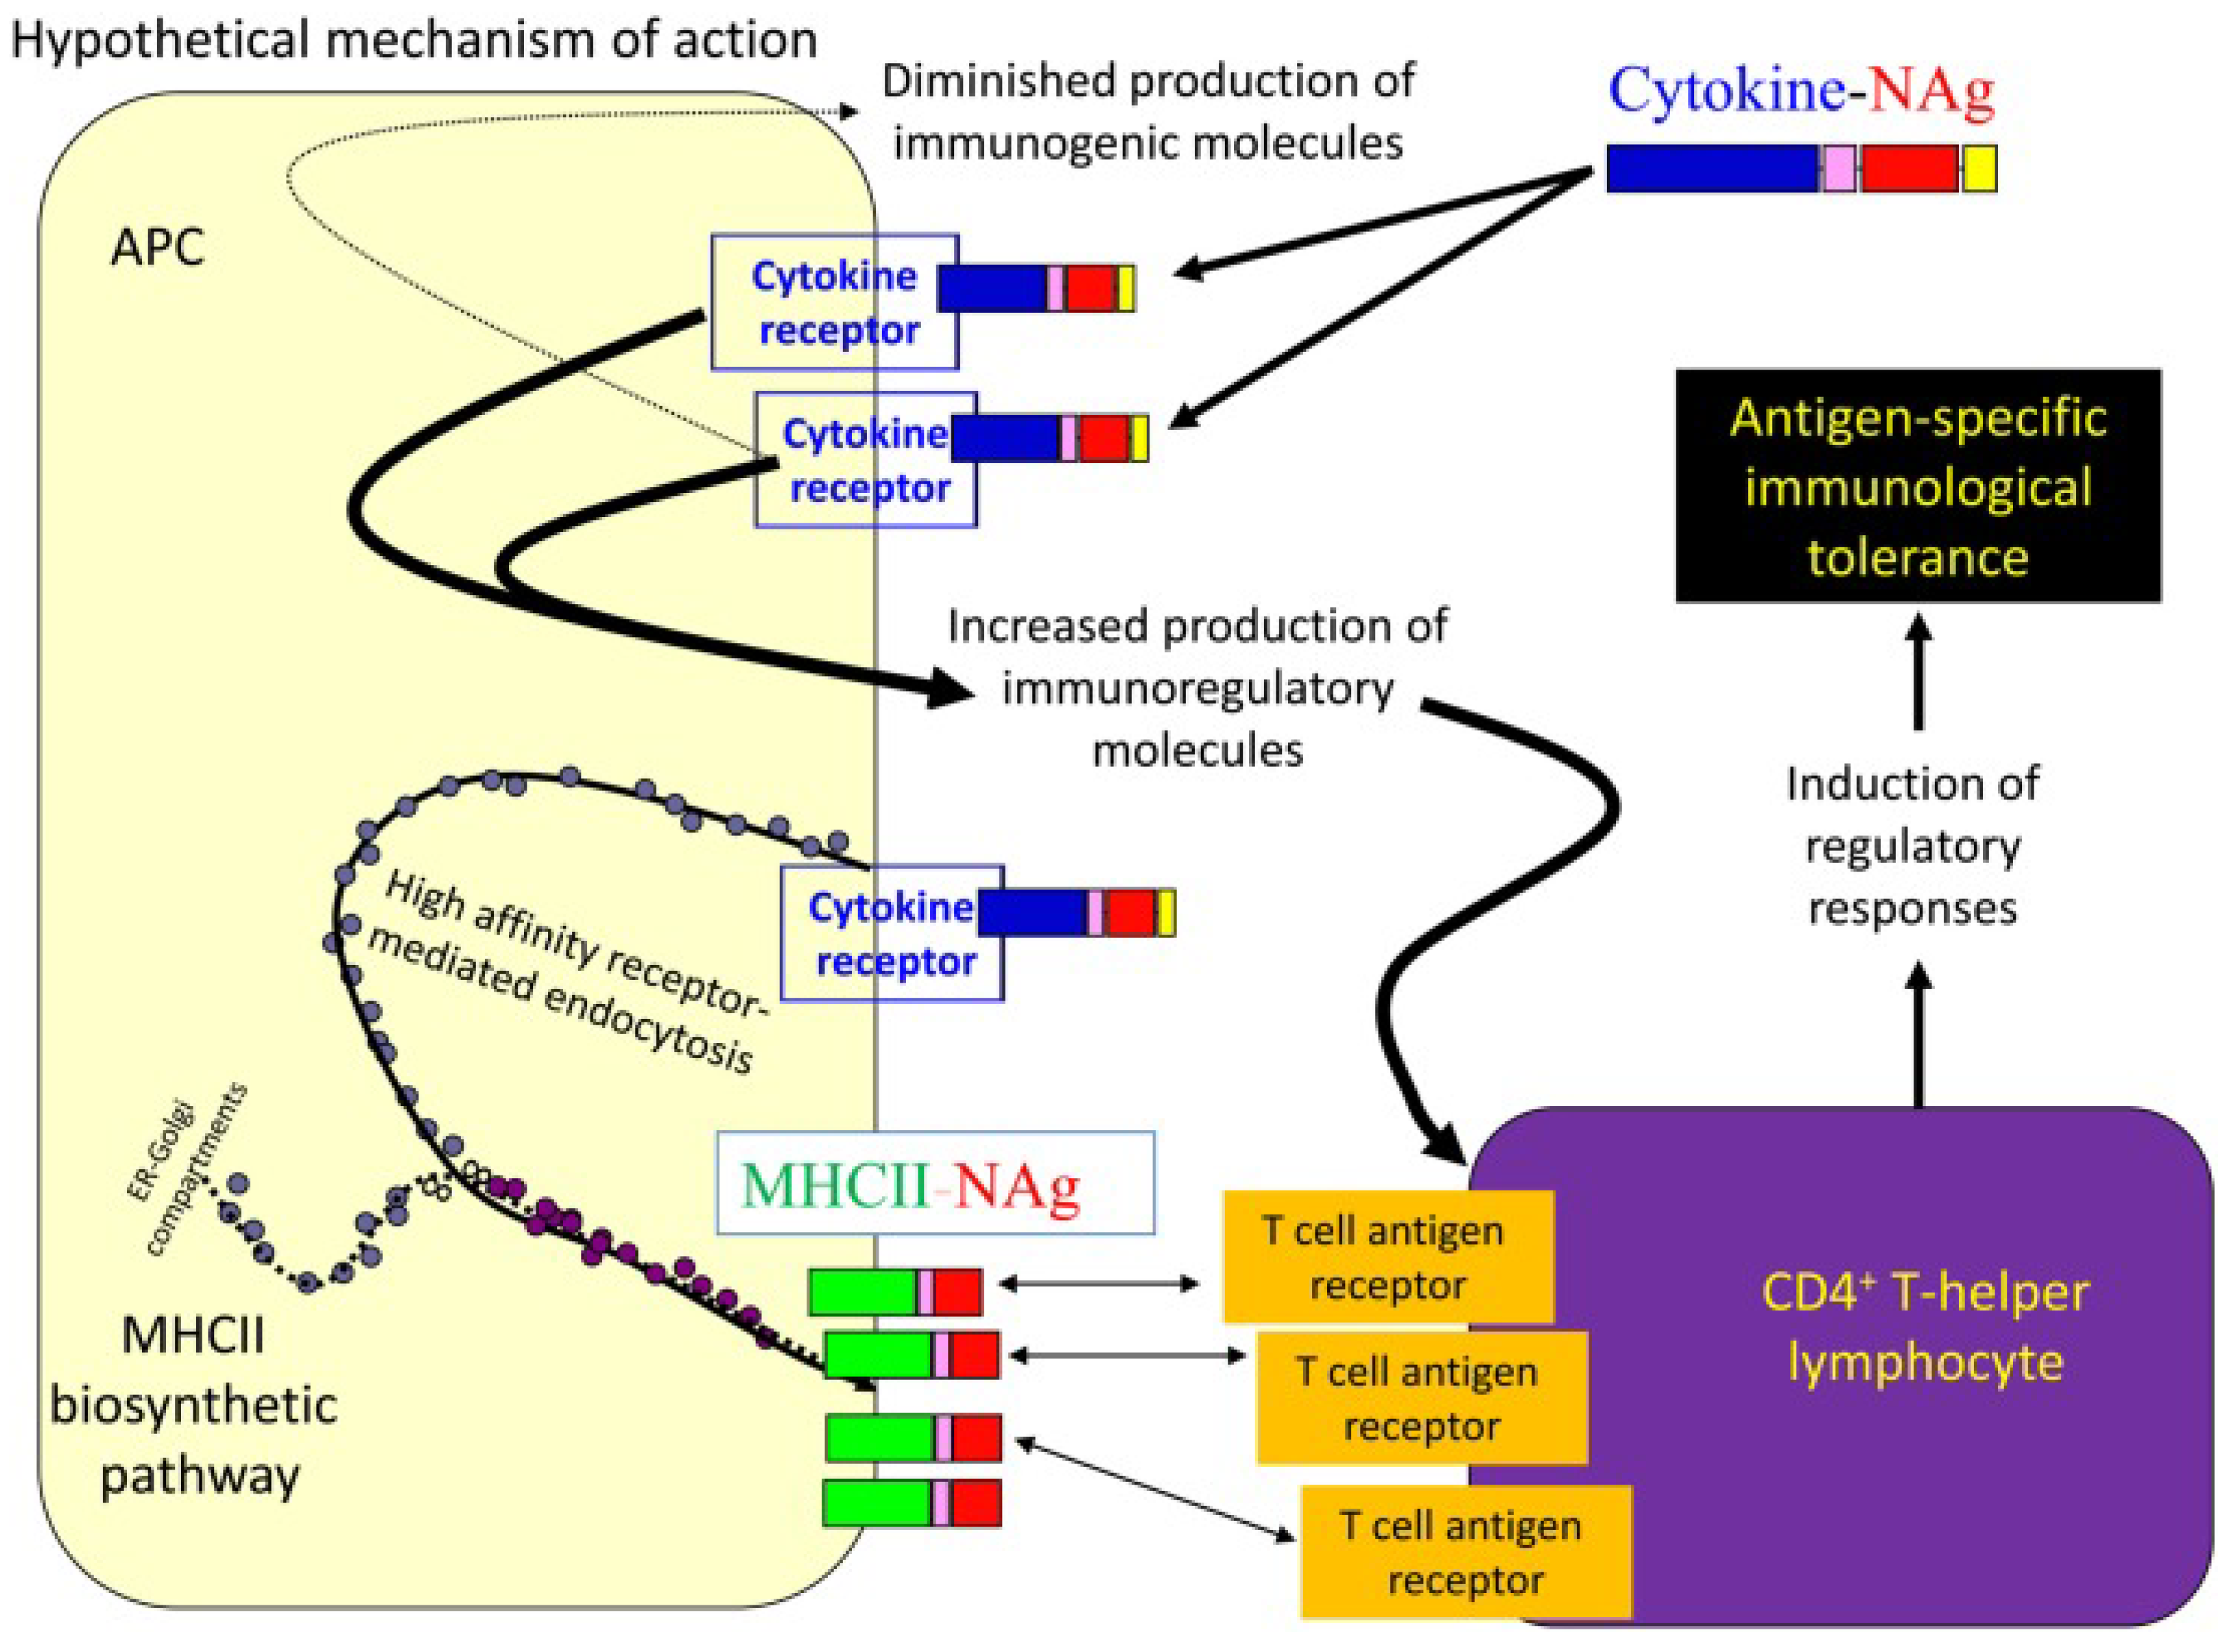
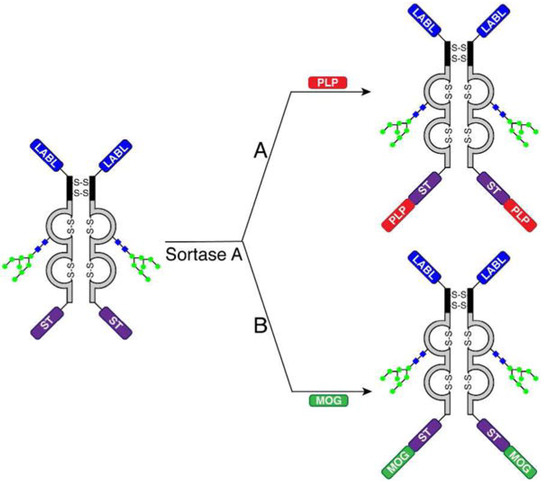
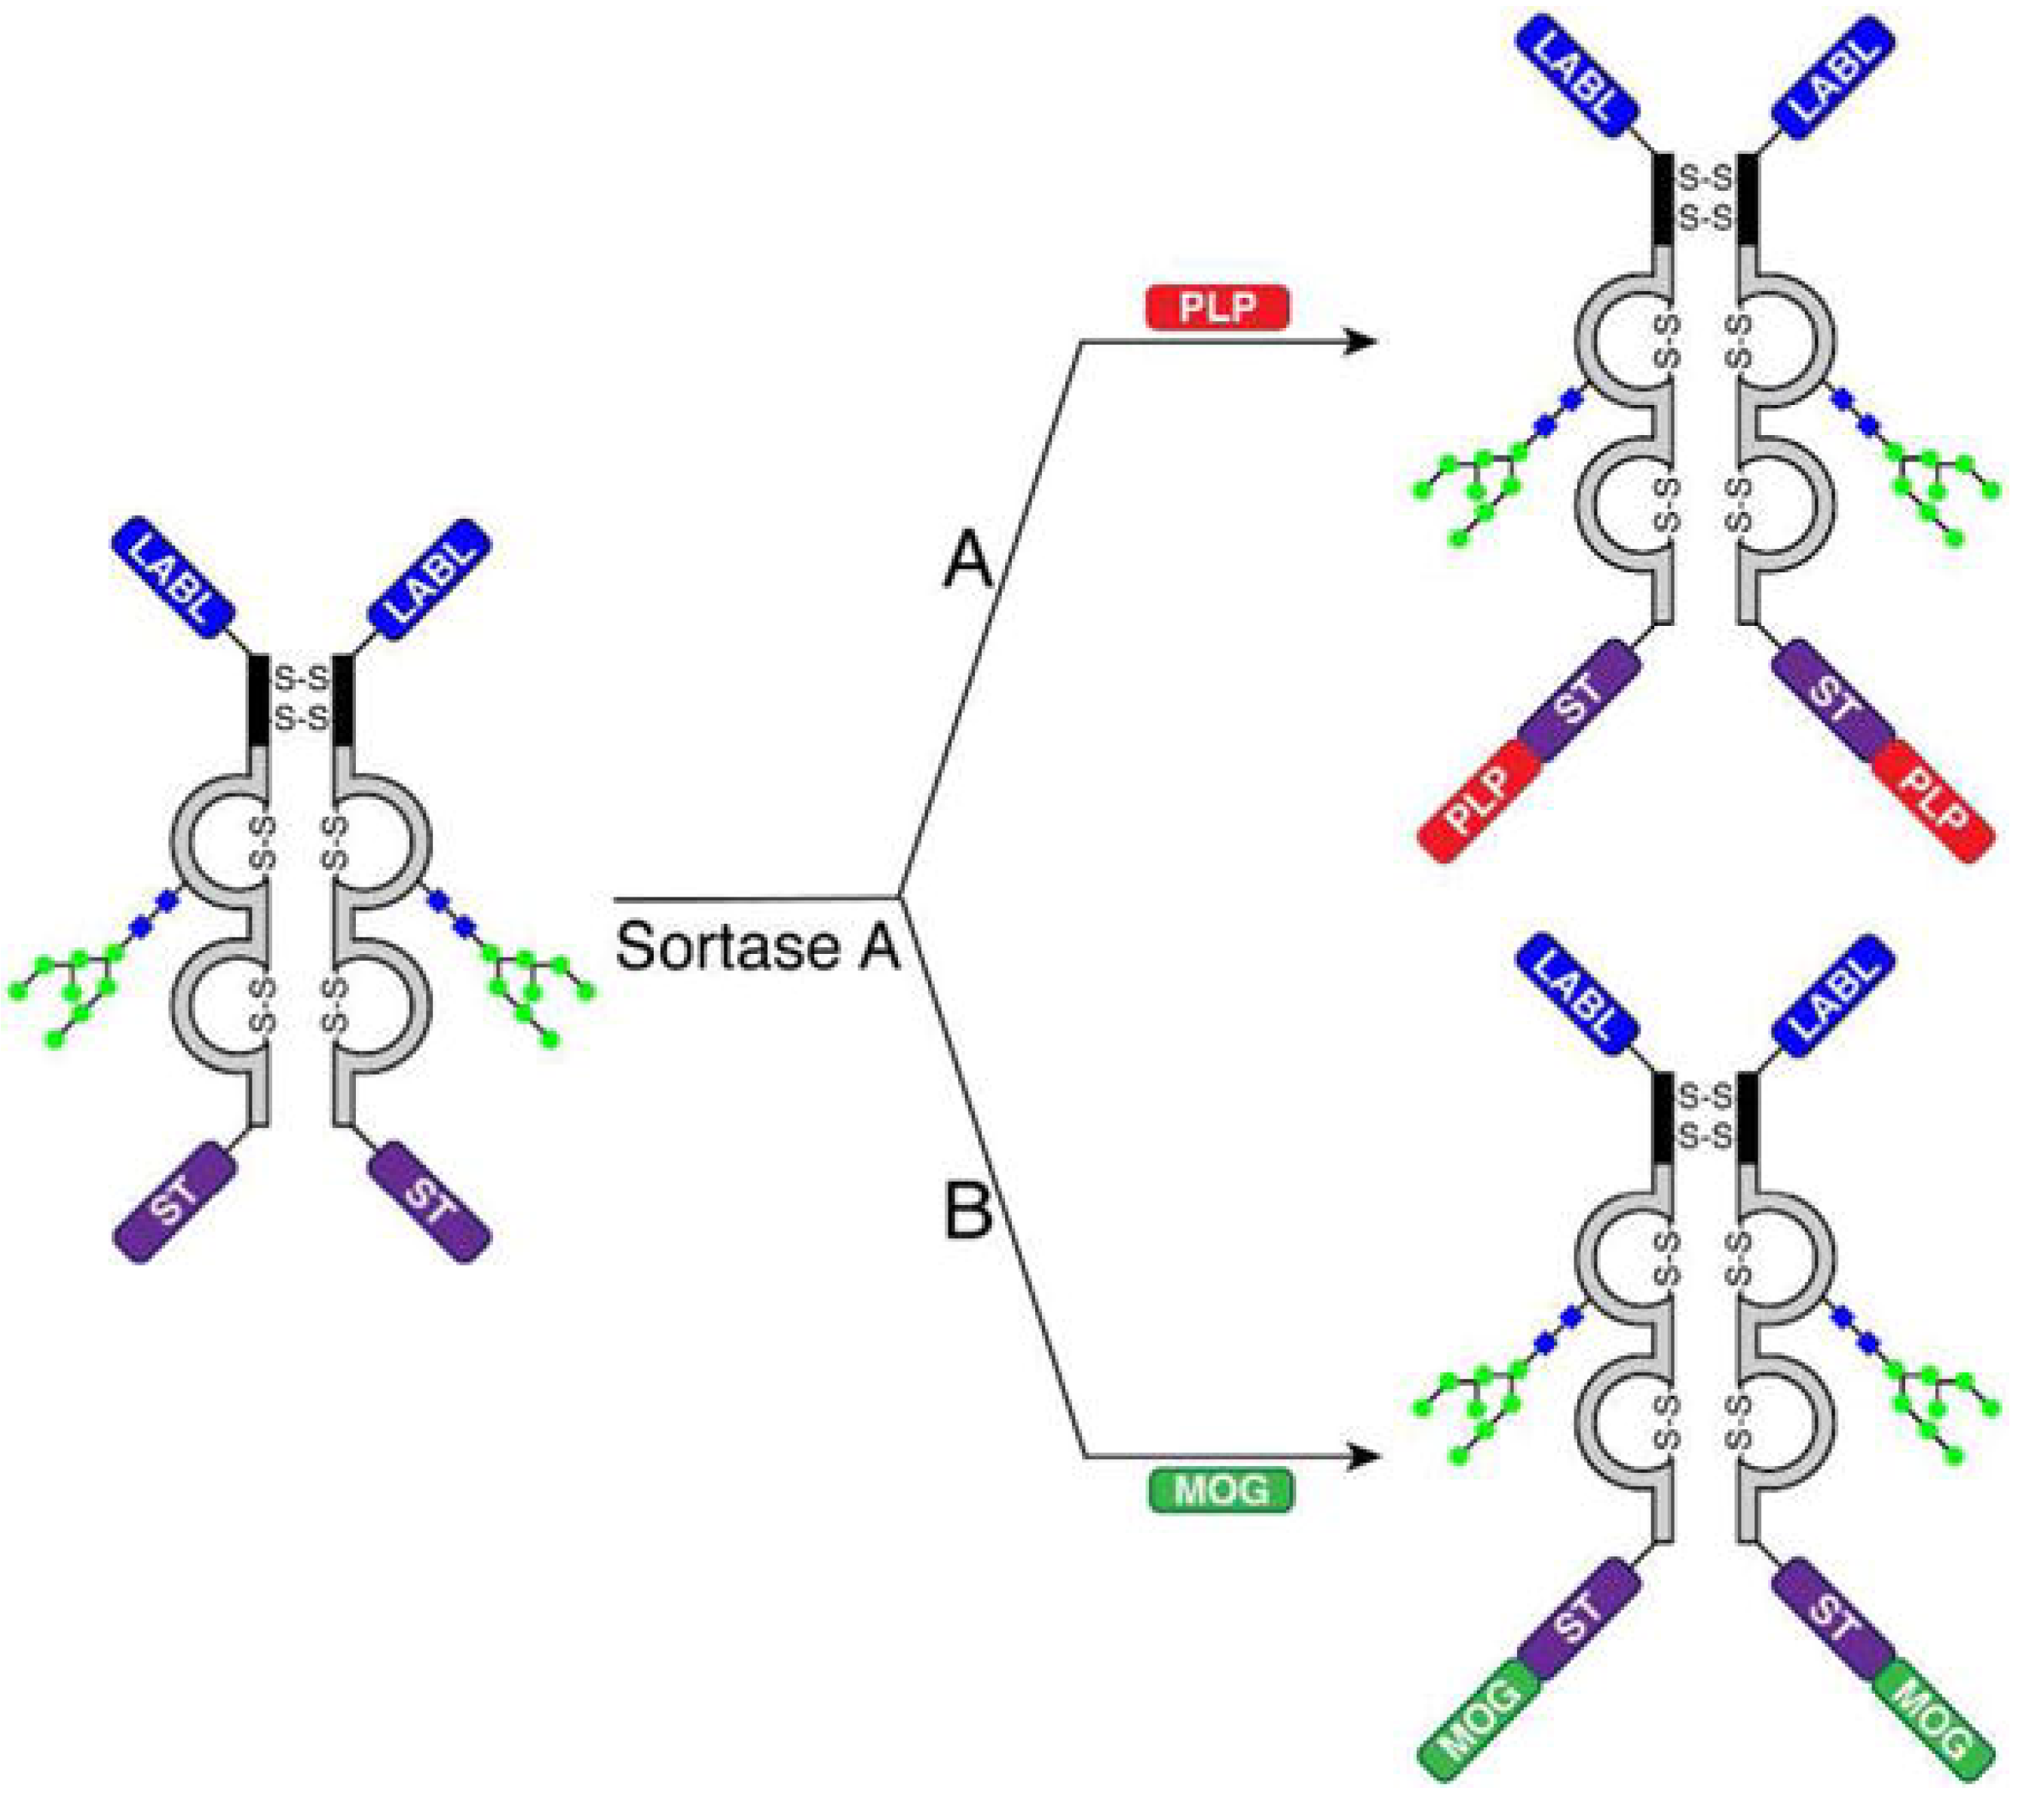
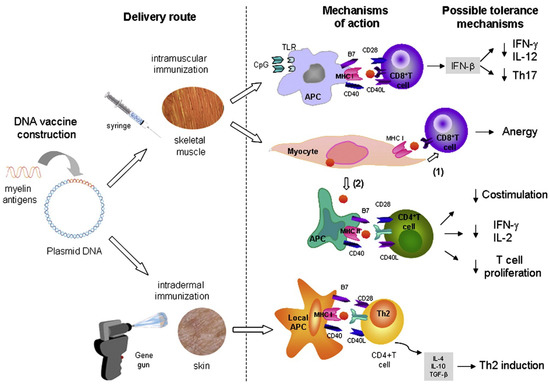
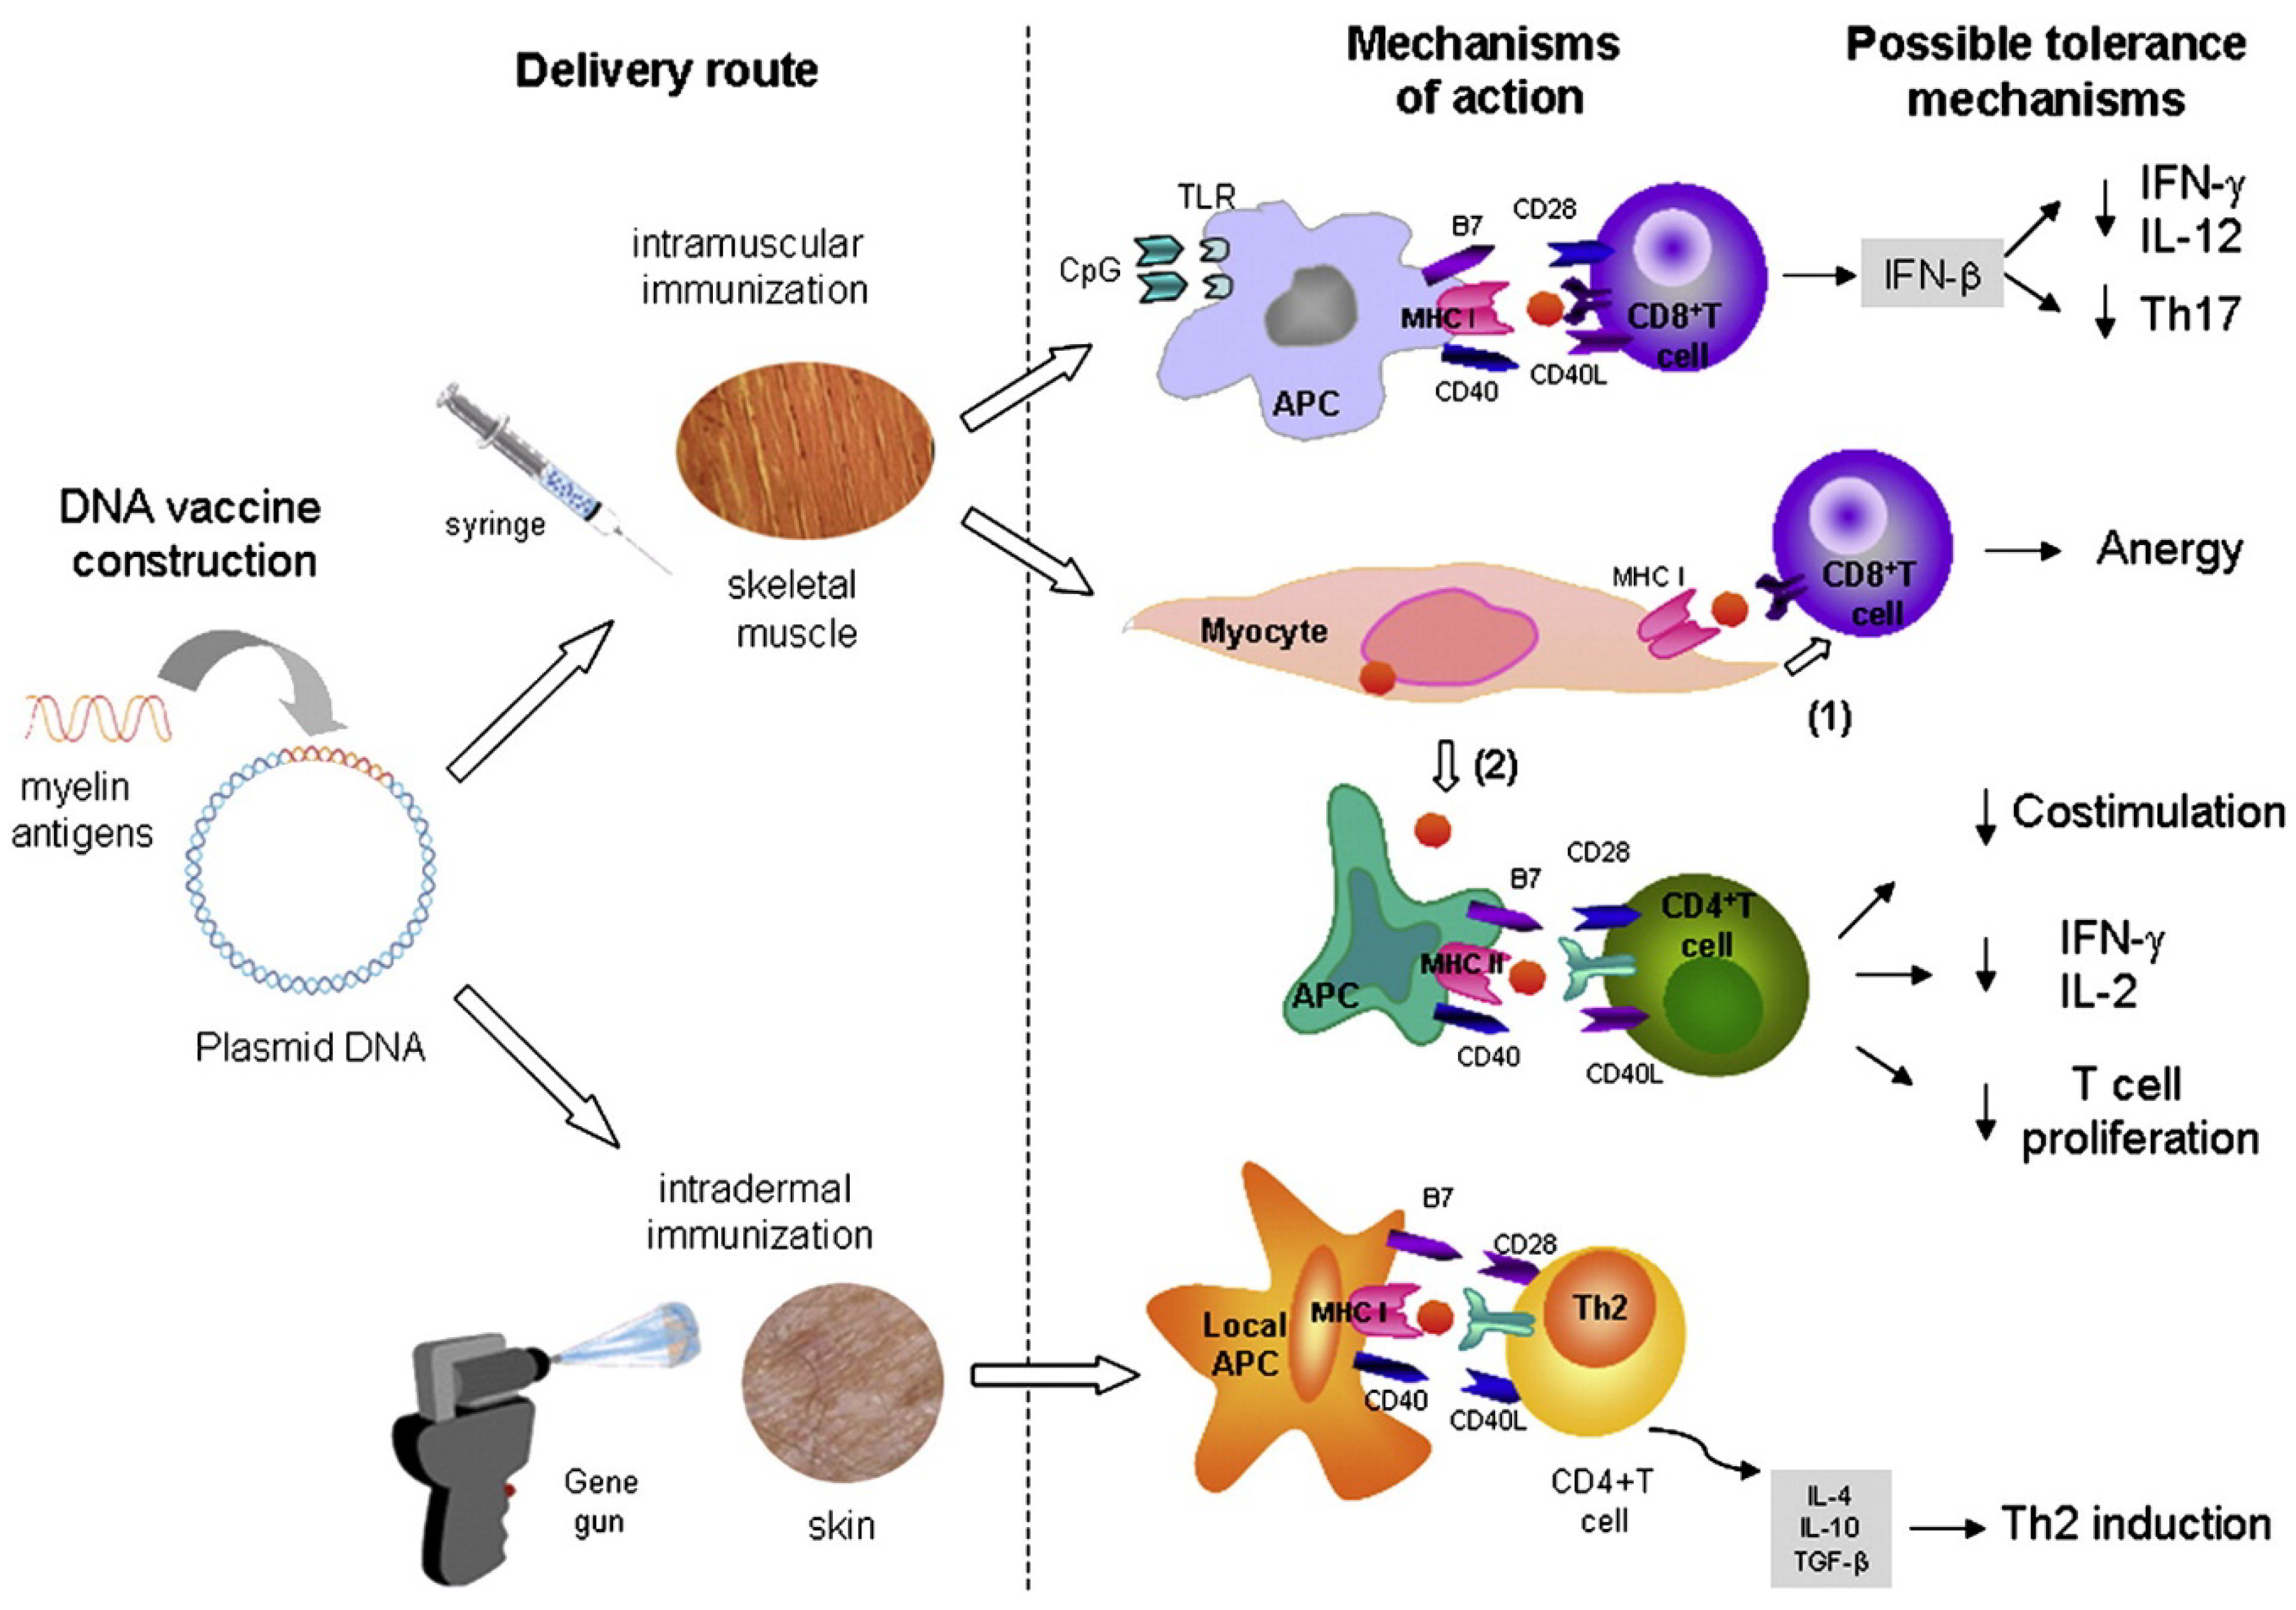
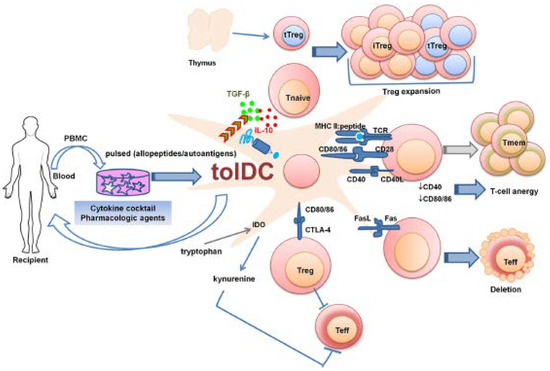
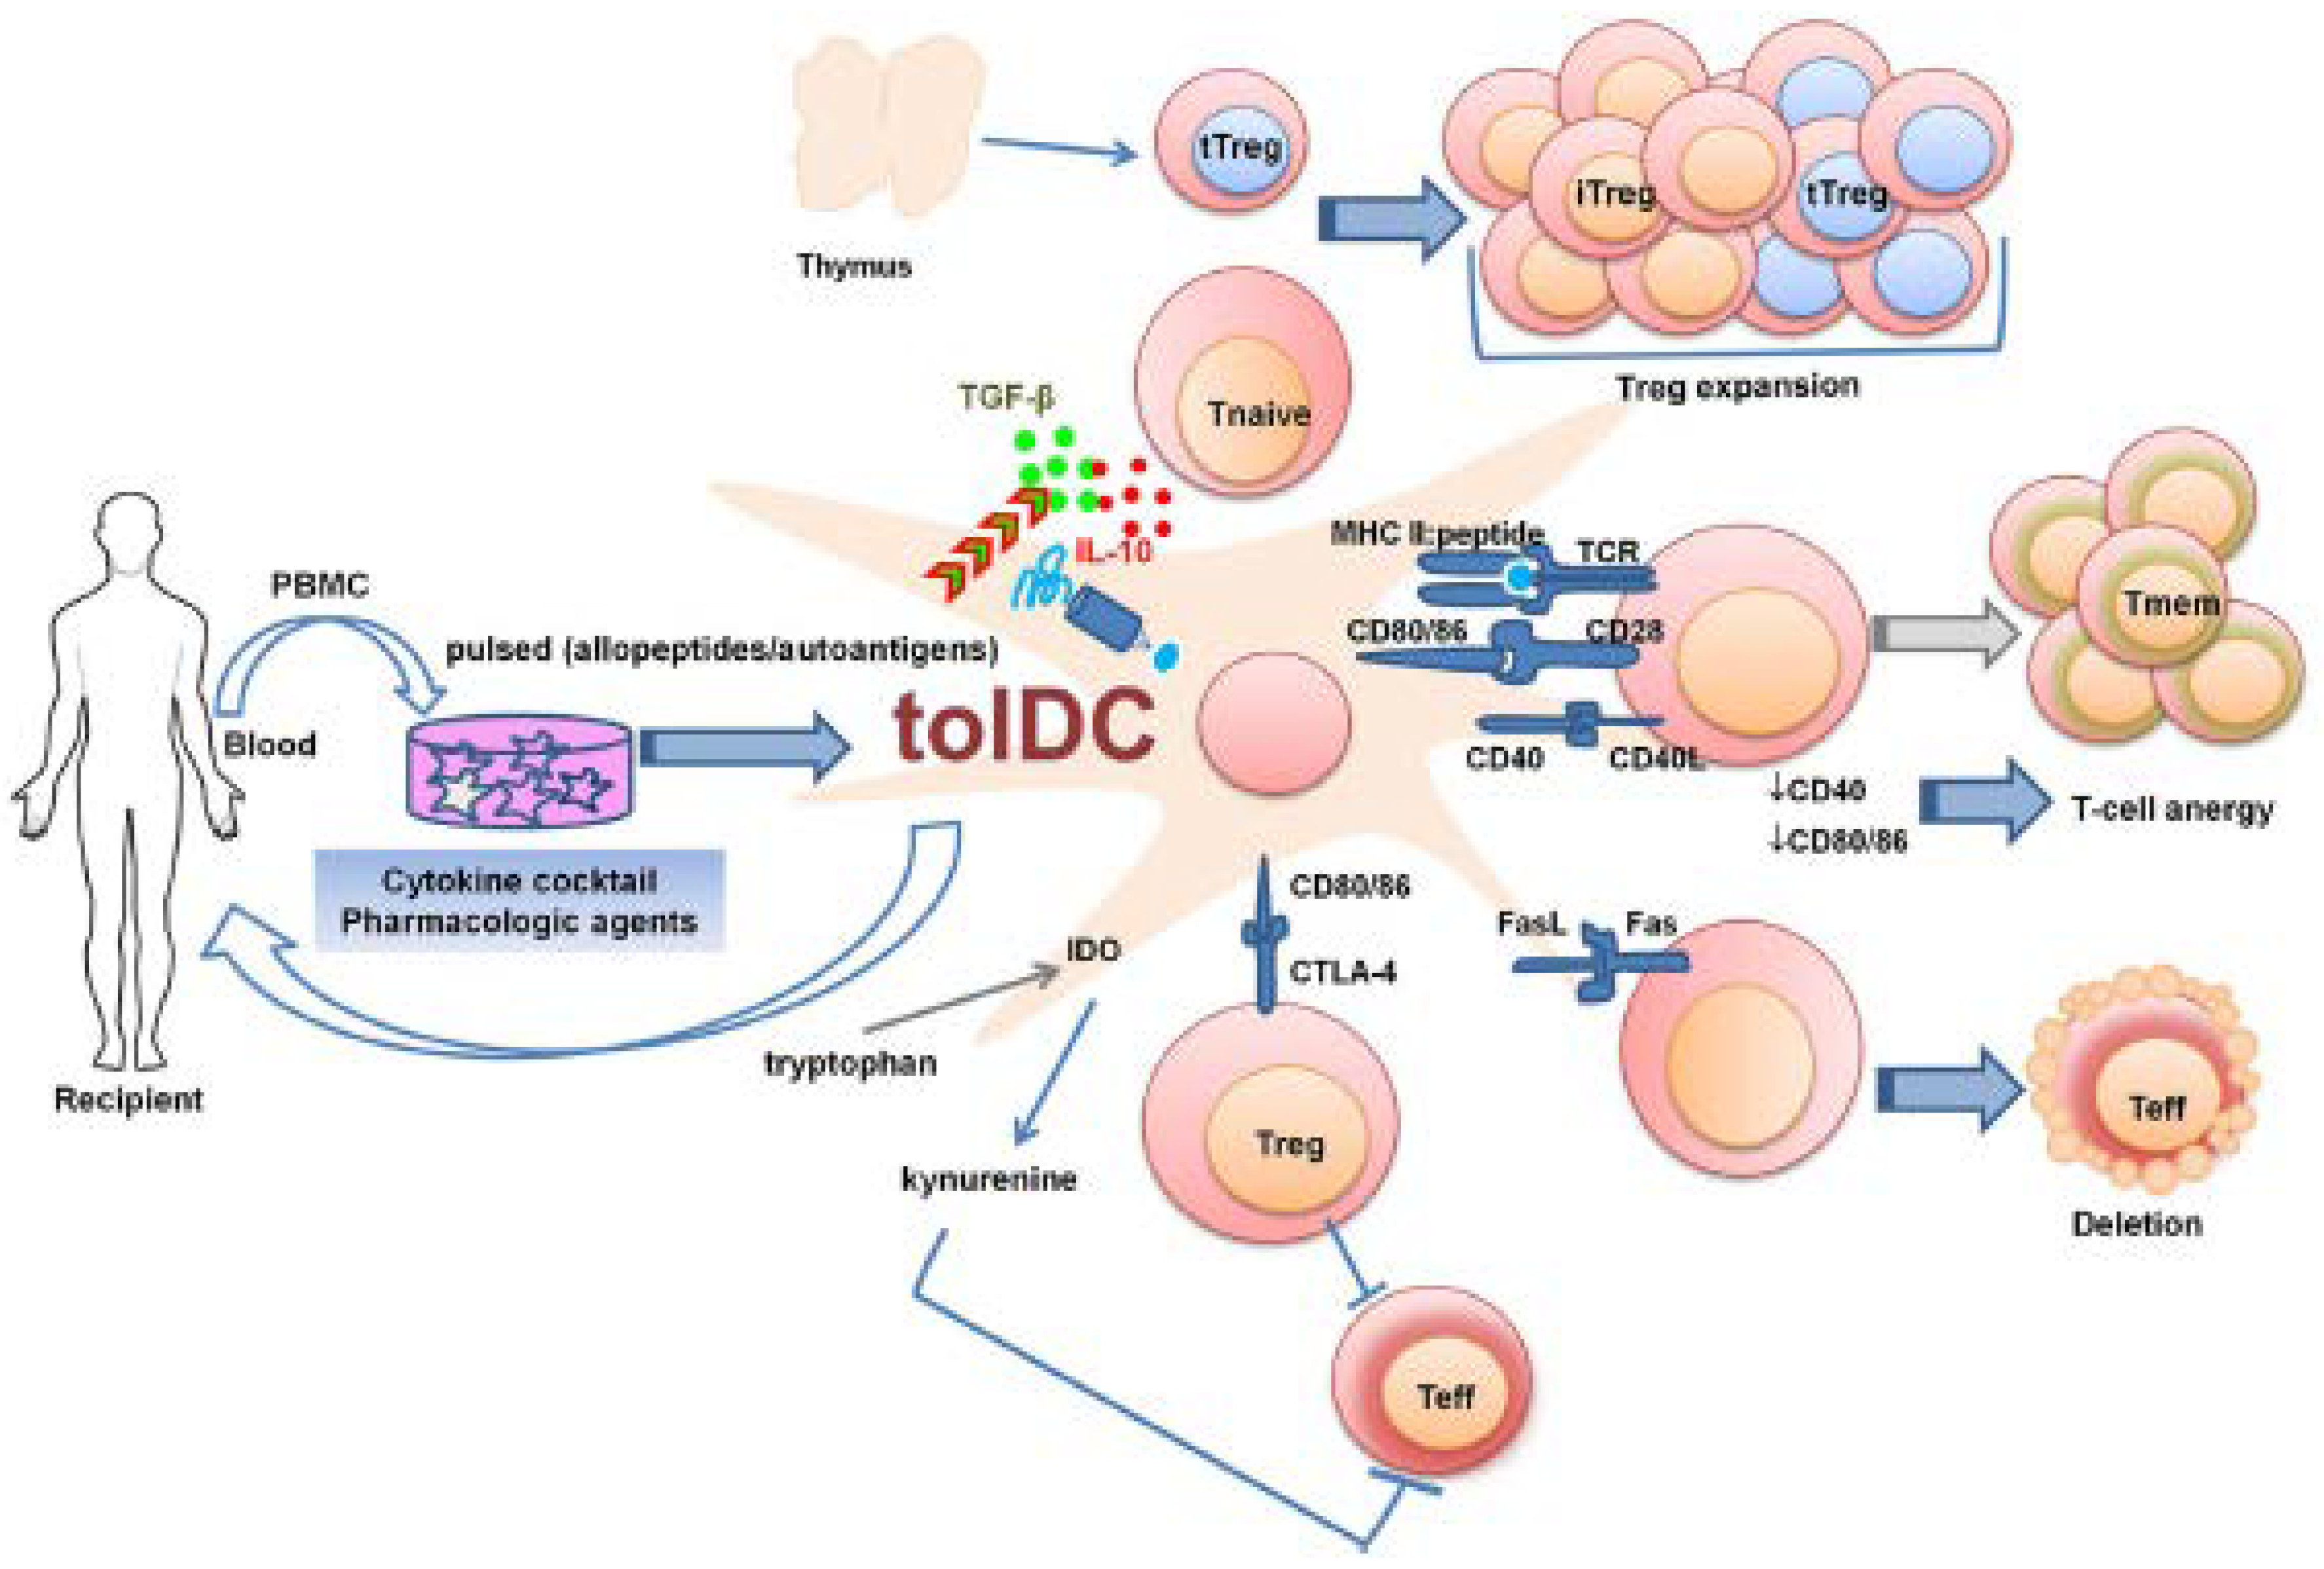
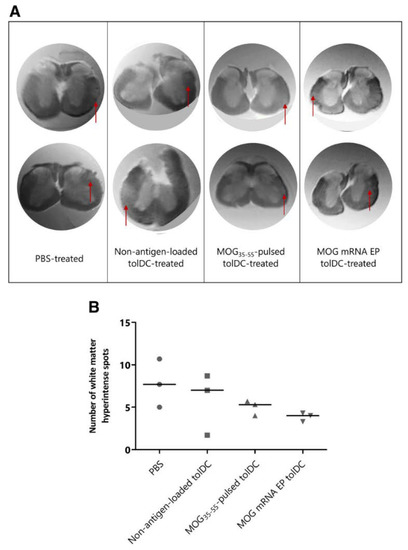
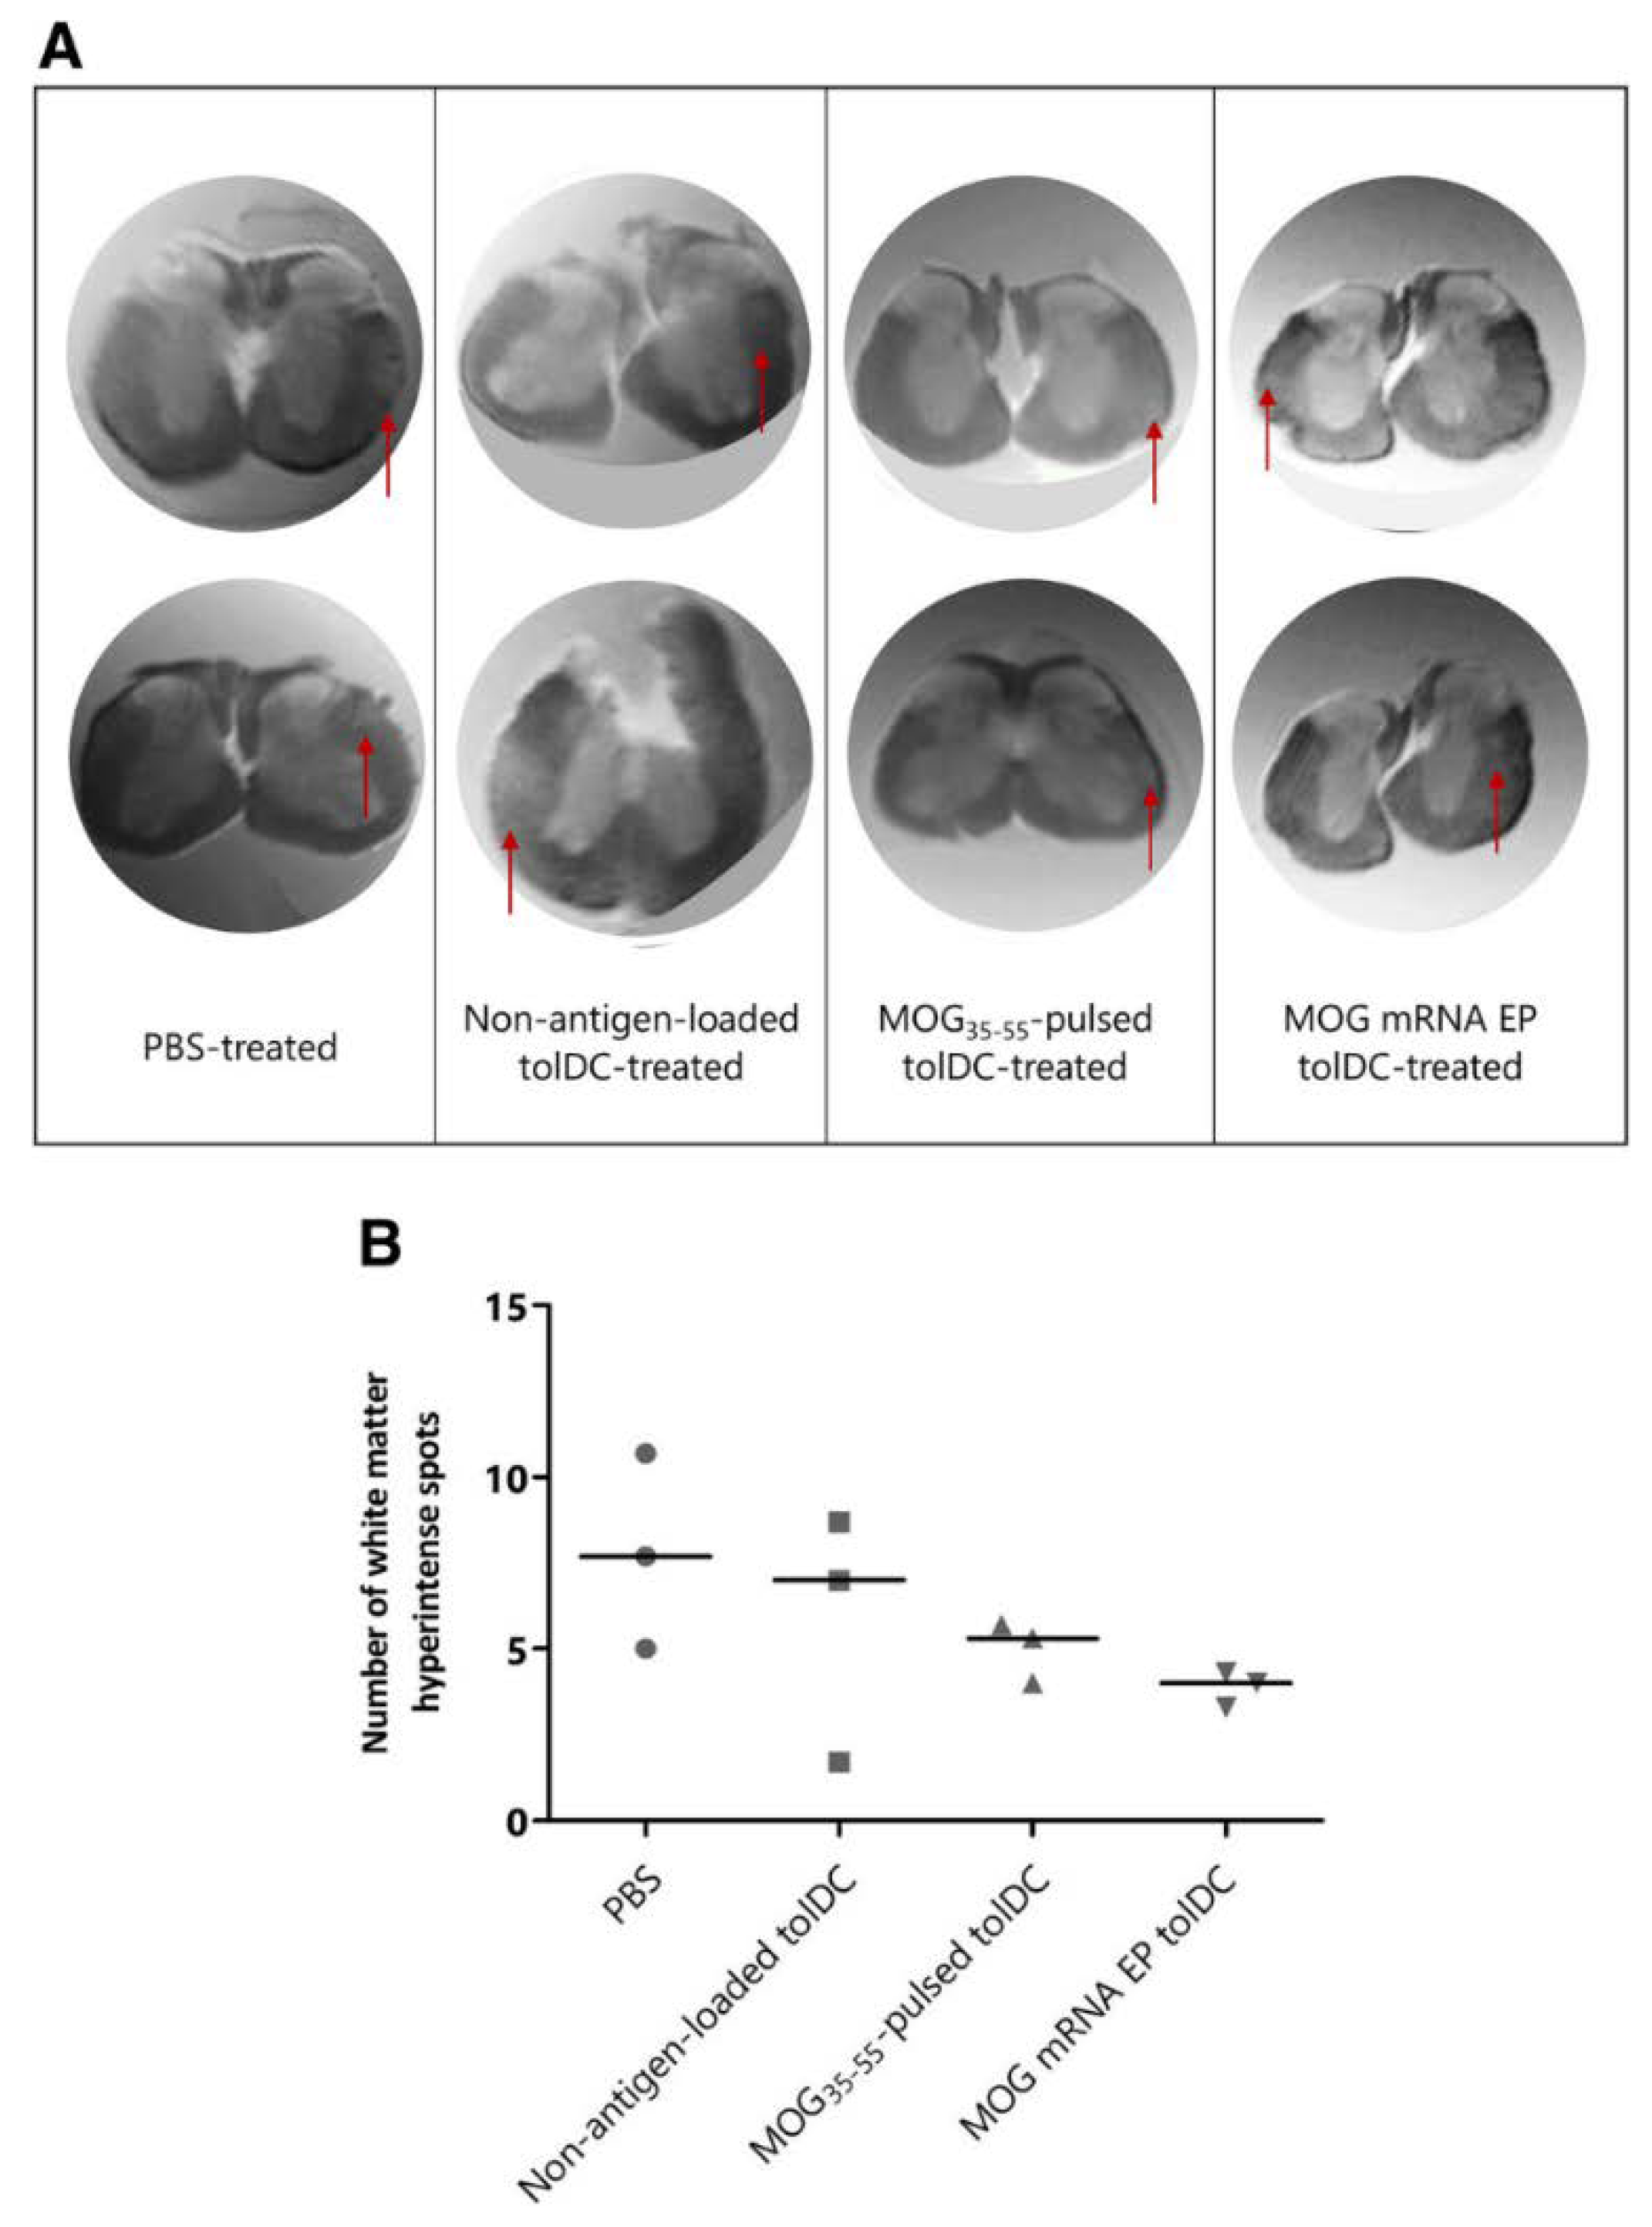
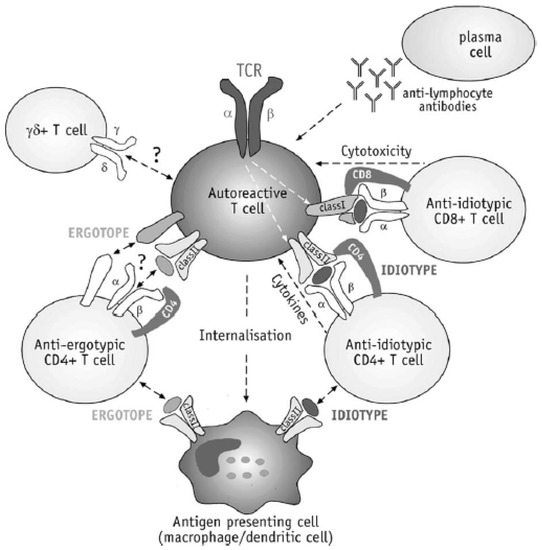
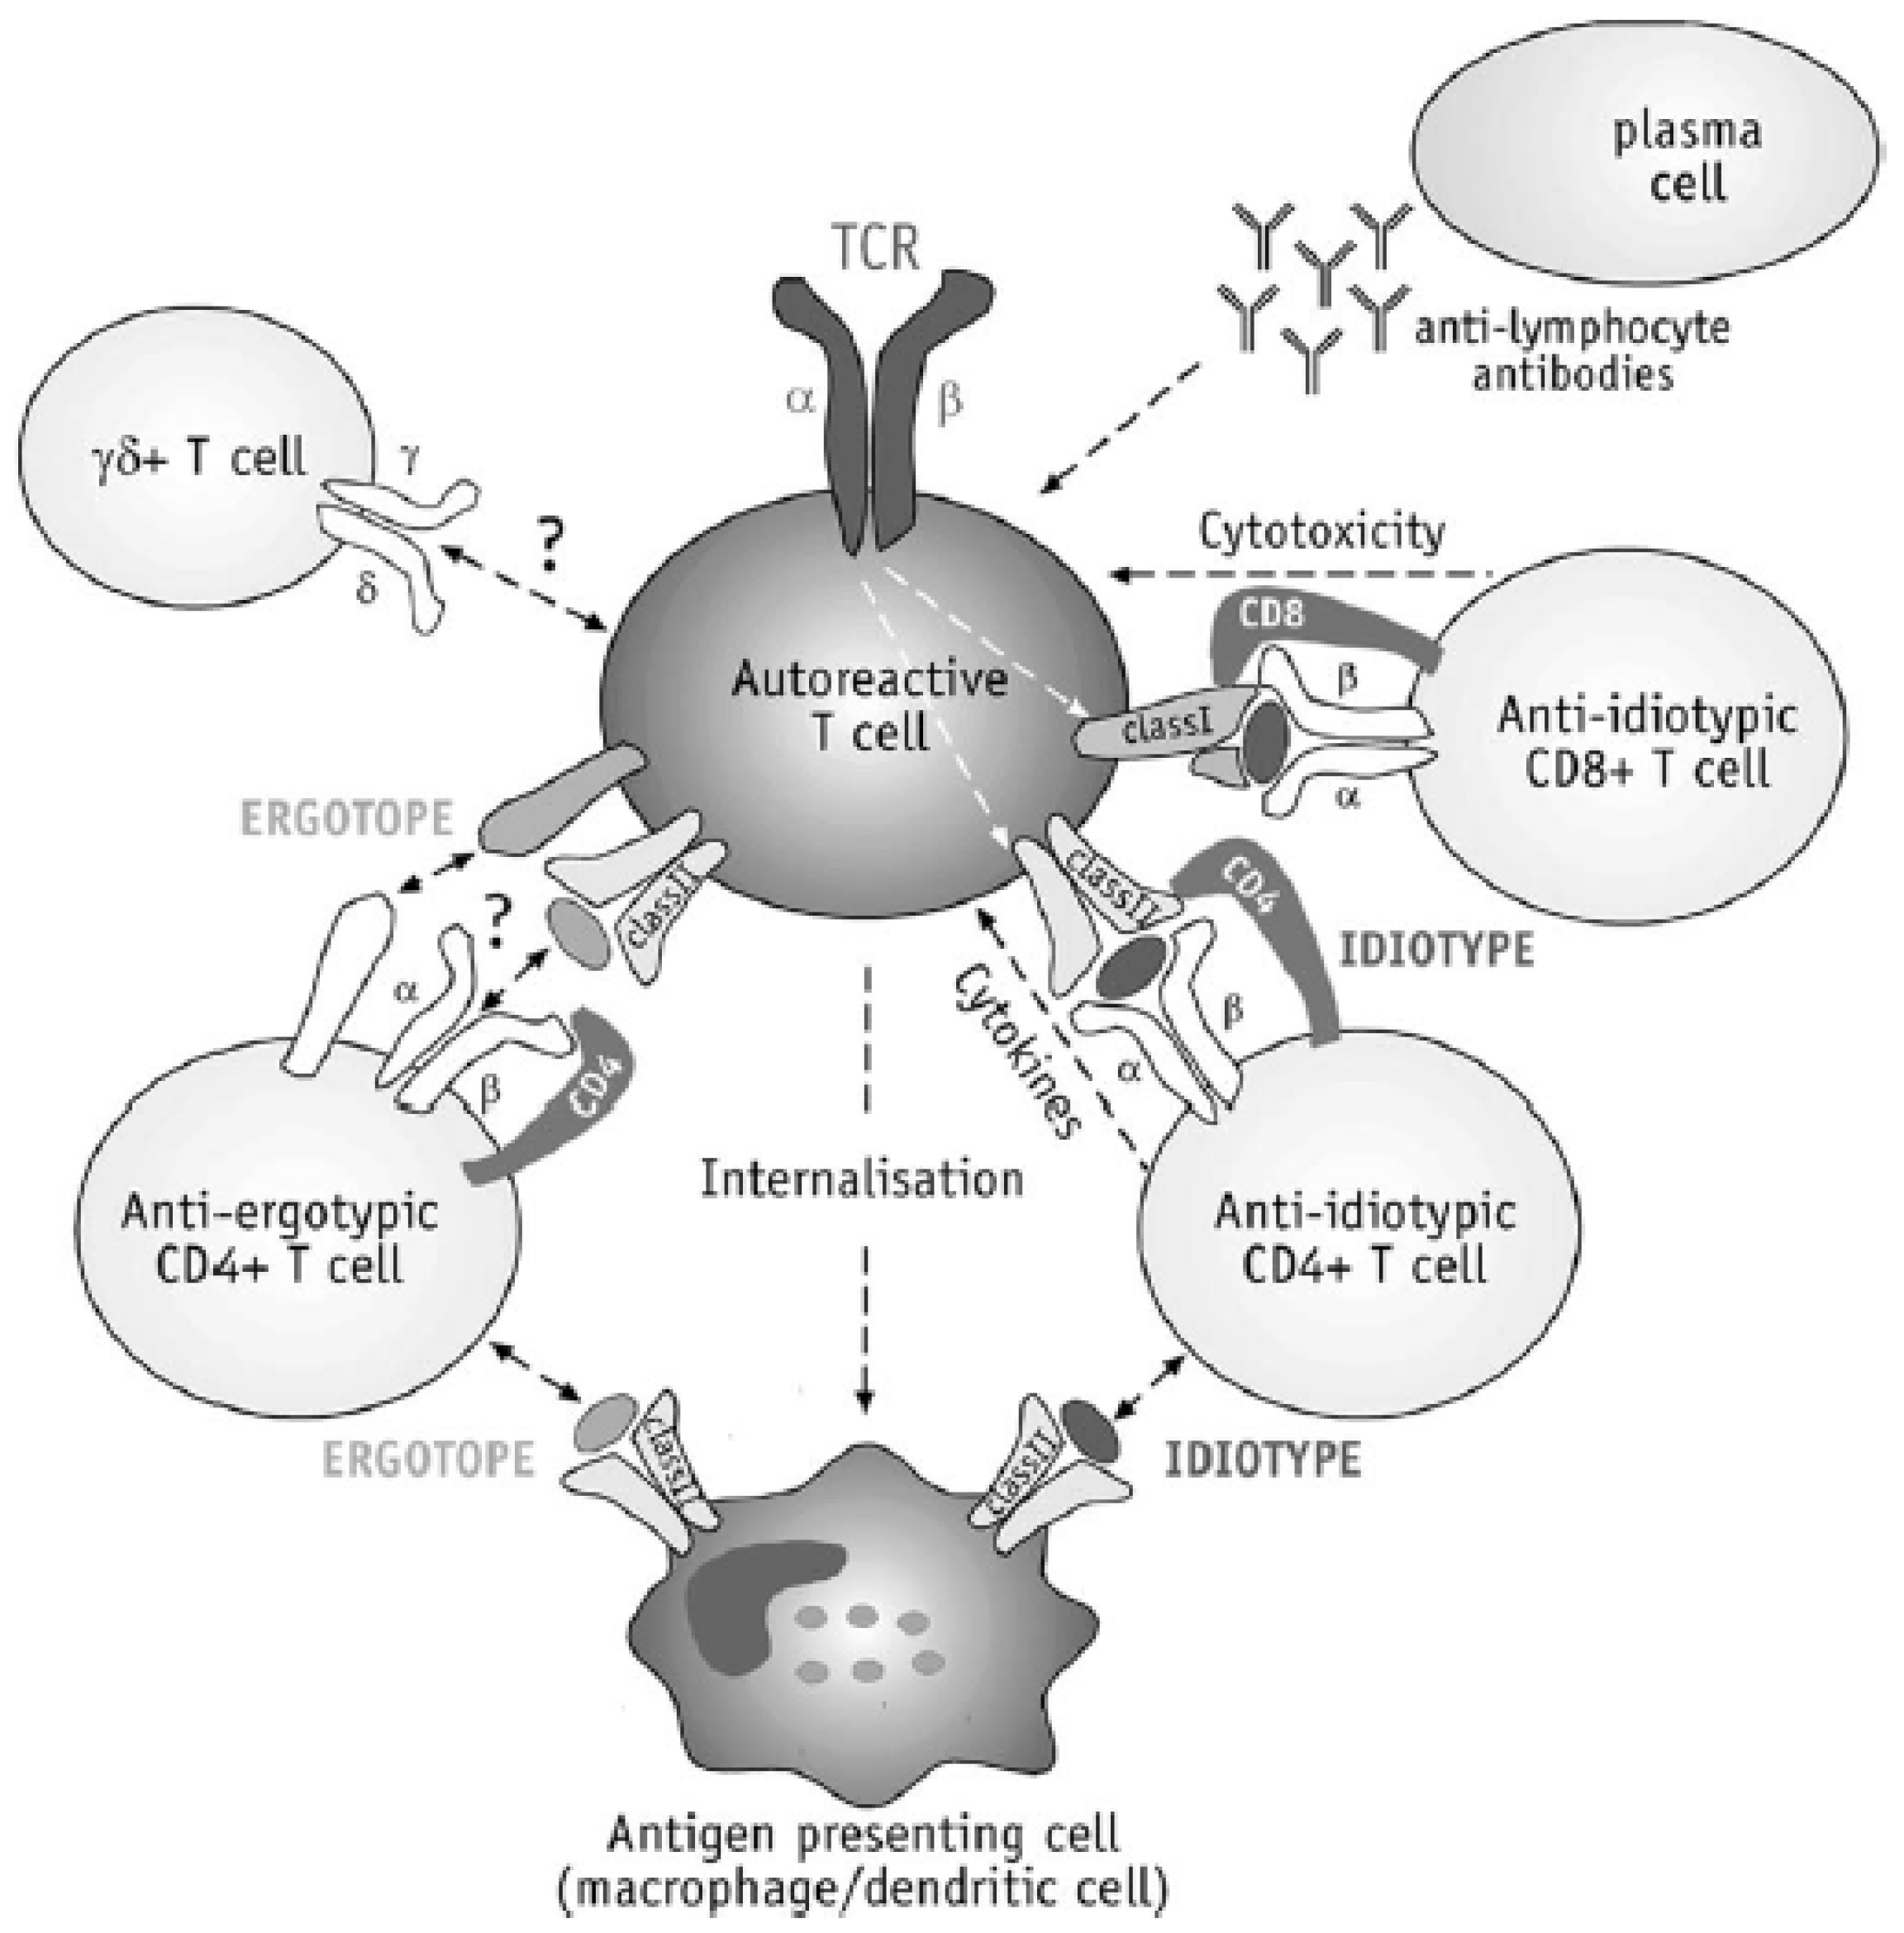
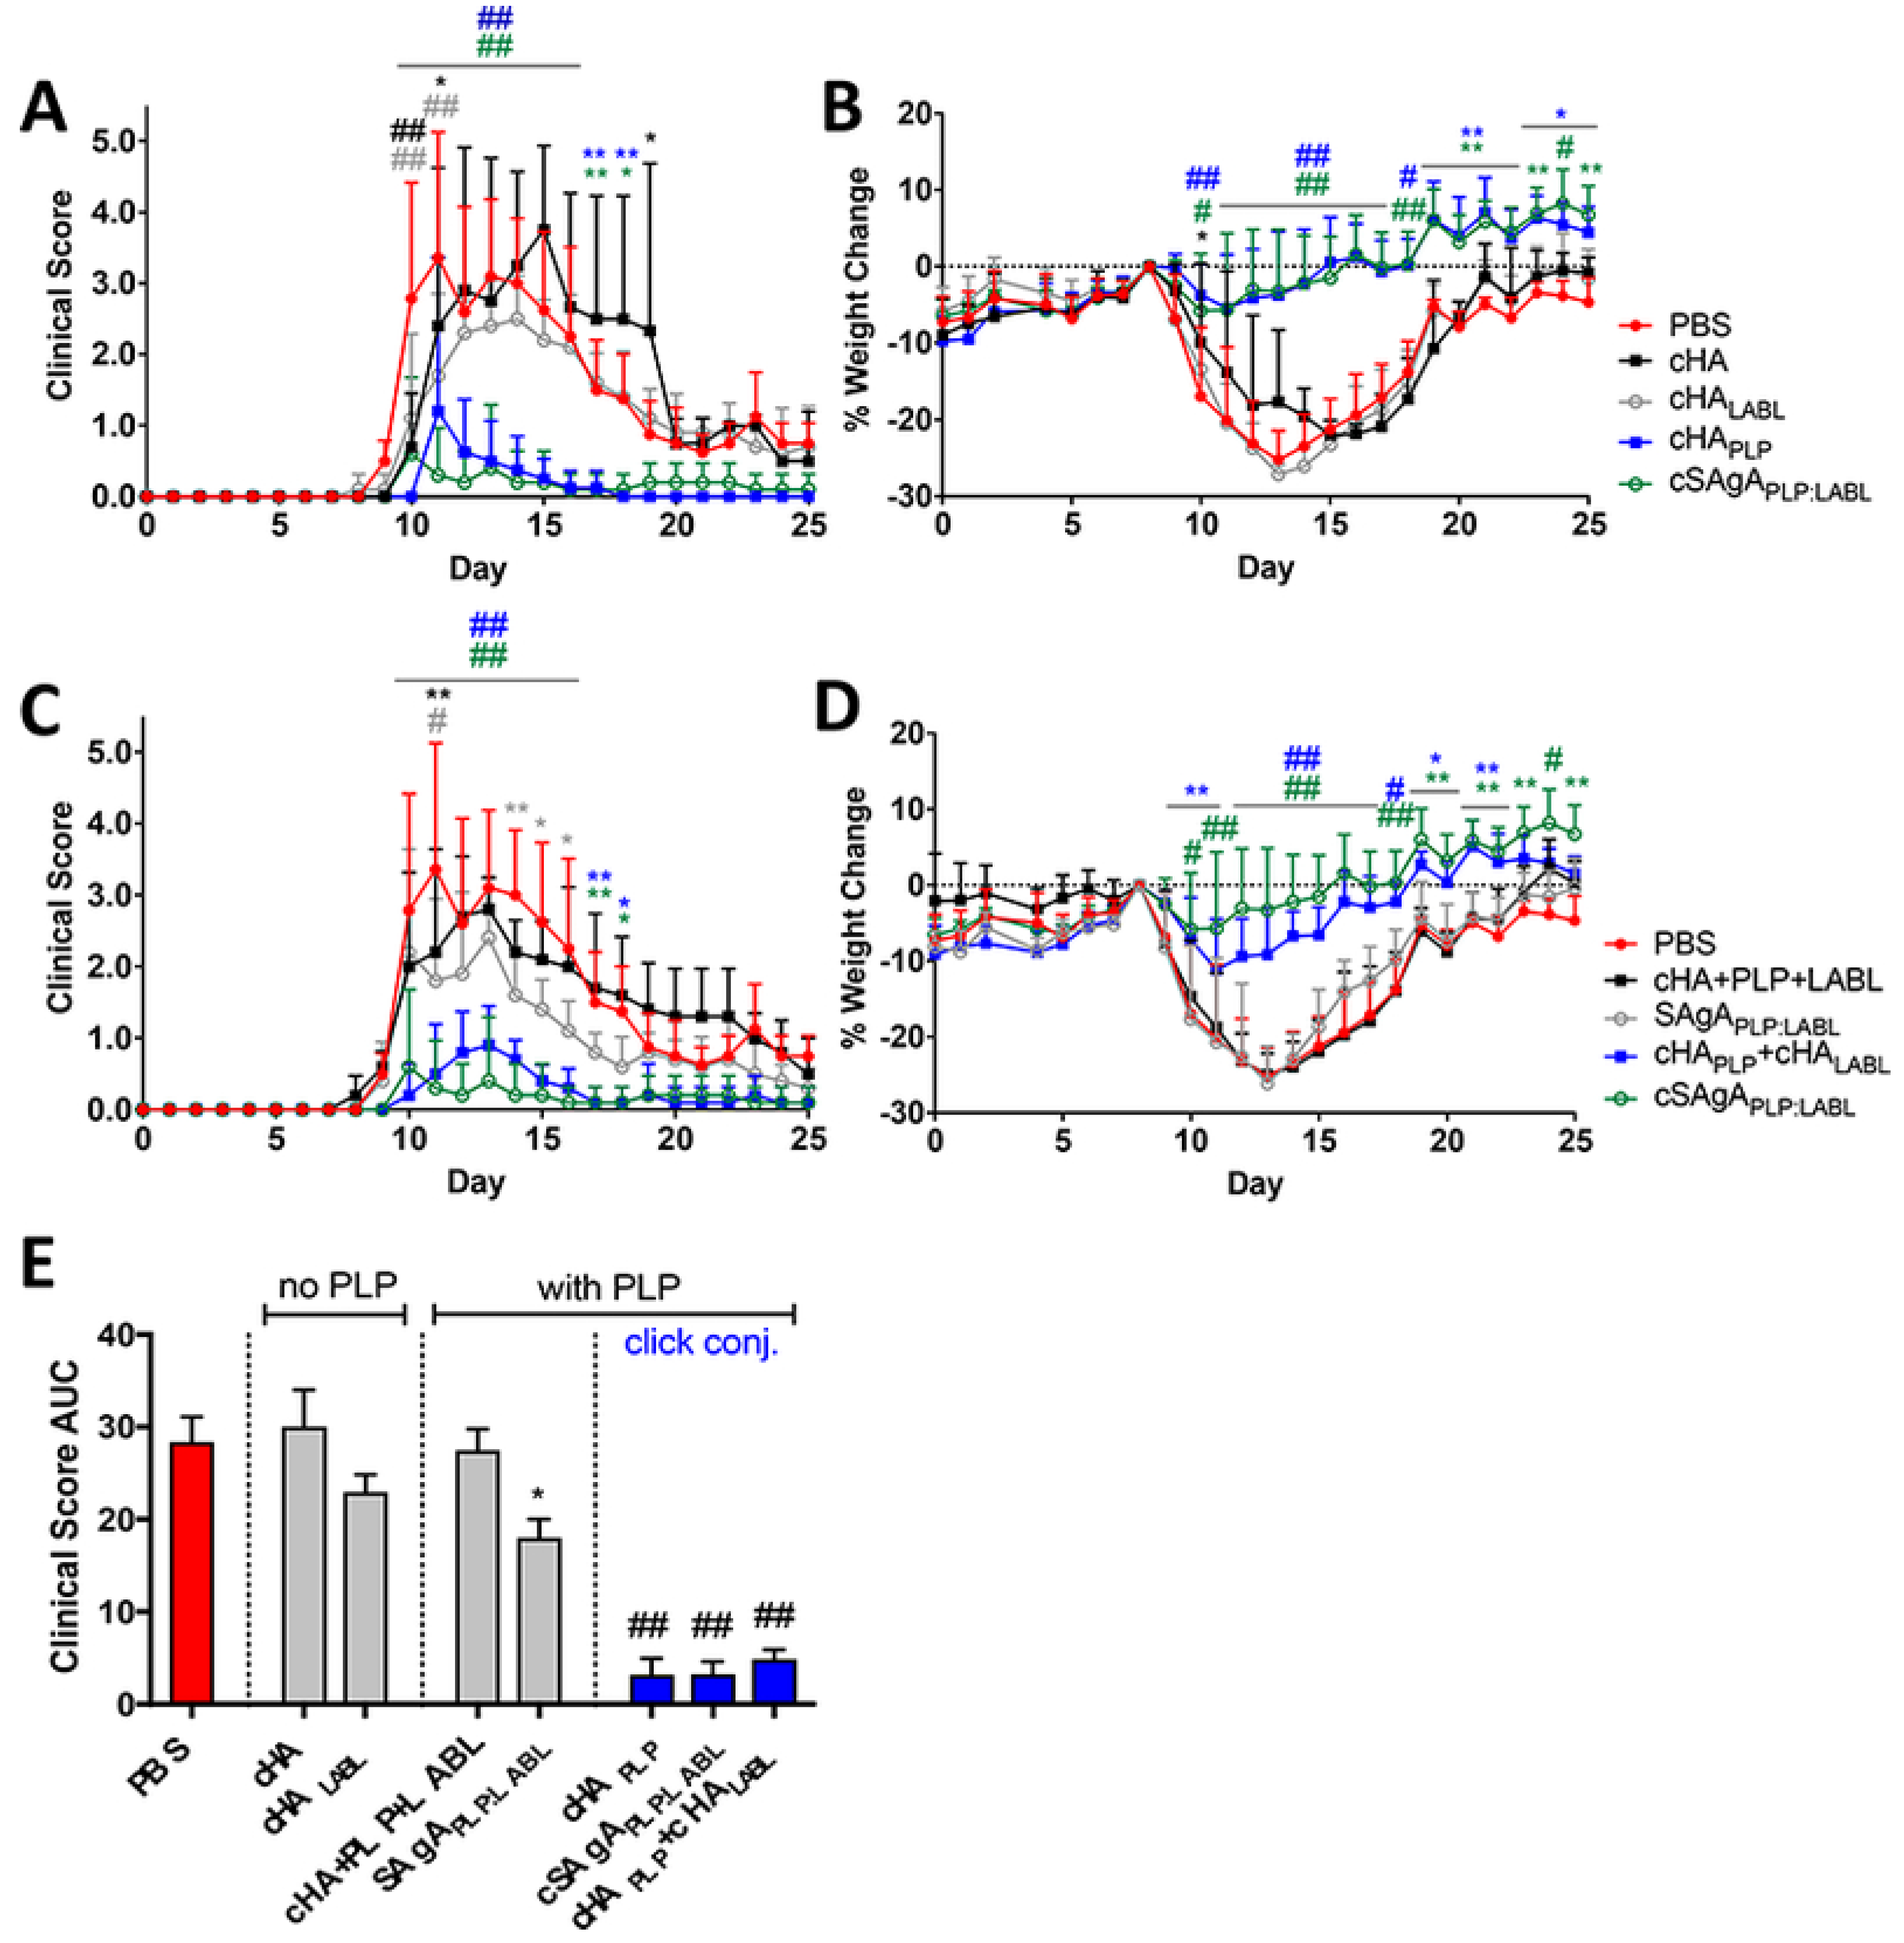
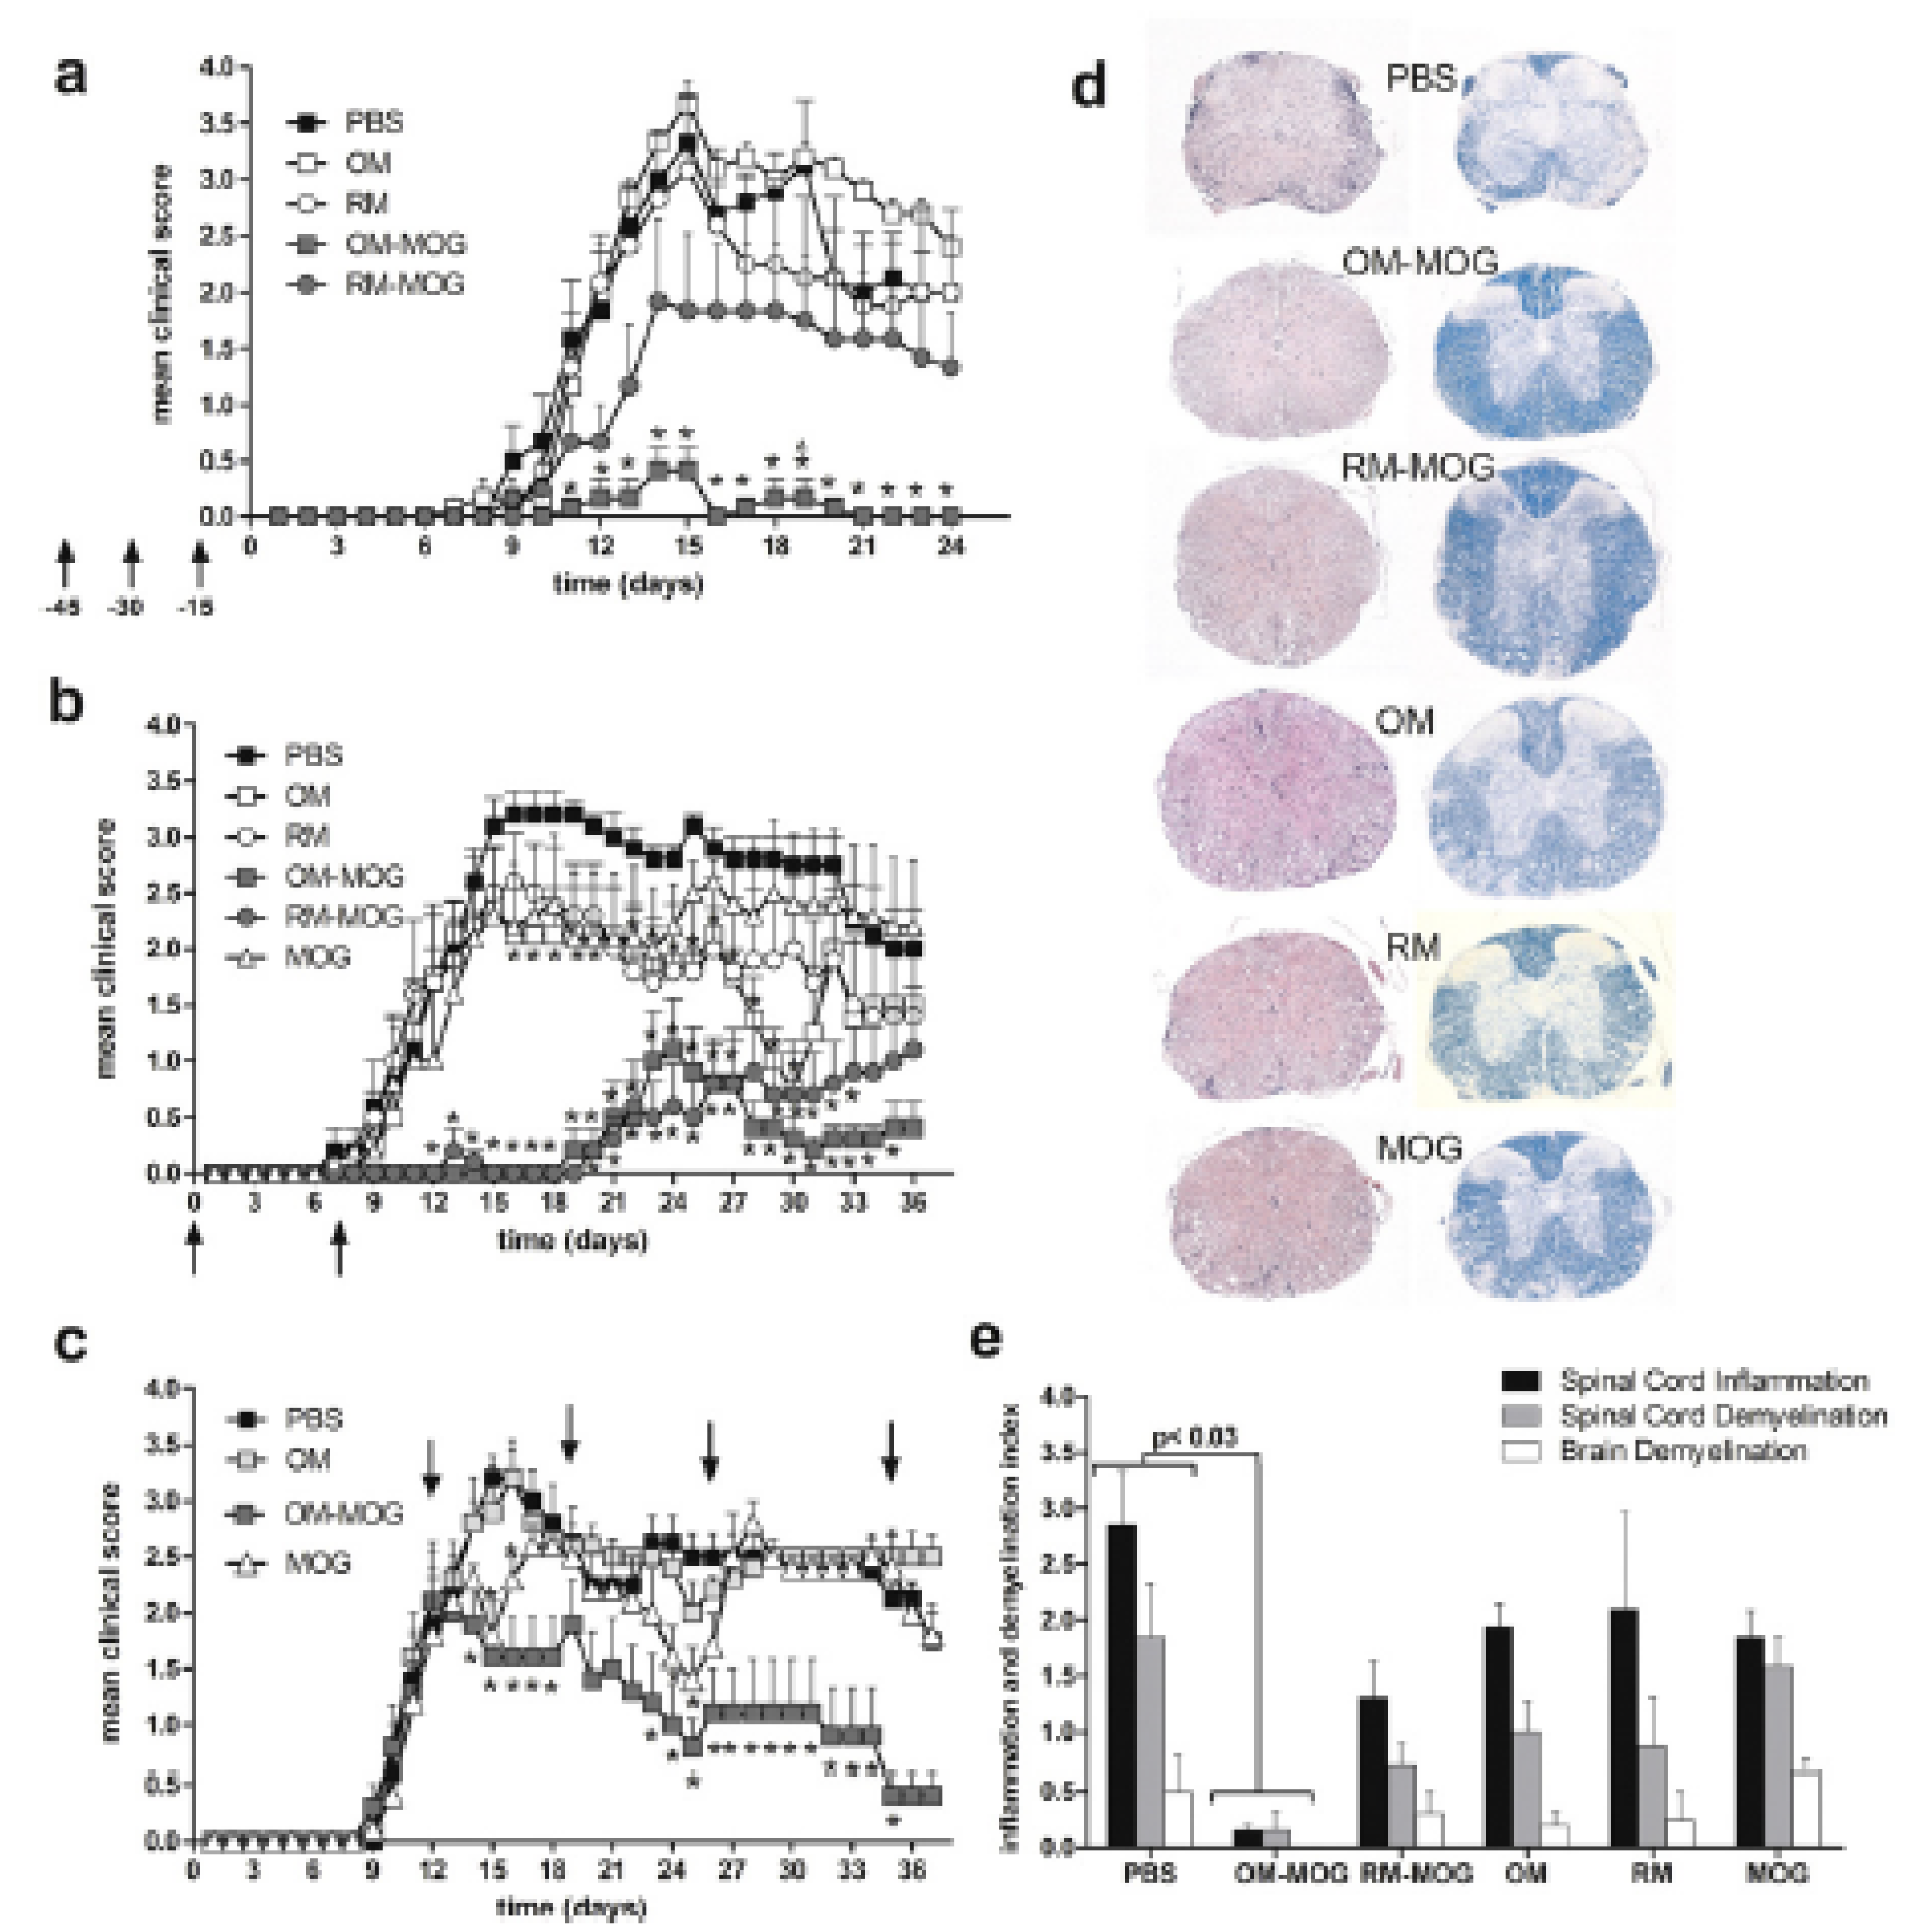

© 2020 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).