


Abstract
(1) Introduction: To develop evidence-based algorithms for targeted antibiotic therapy of infections caused by Staphylococcus aureus in critically ill adult patients. (2) Methods: A multidisciplinary team of four experts had several rounds of assessment for developing algorithms concerning targeted antimicrobial therapy of severe infections caused by Staphylococcus aureus in critically ill patients. The literature search was performed by a researcher on PubMed-MEDLINE (until August 2022) to provide evidence for supporting therapeutic choices. Quality and strength of evidence was established according to a hierarchical scale of the study design. Two different algorithms were created, one for methicillin-susceptible Staphylococcus aureus (MSSA) and the other for methicillin-resistant Staphylococcus aureus (MRSA). The therapeutic options were categorized for each different site of infection and were selected also on the basis of pharmacokinetic/pharmacodynamic features. (3) Results: Cefazolin or oxacillin were the agents proposed for all of the different types of severe MSSA infections. The proposed targeted therapies for severe MRSA infections were different according to the infection site: daptomycin plus fosfomycin or ceftaroline or ceftobiprole for bloodstream infections, infective endocarditis, and/or infections associated with intracardiac/intravascular devices; ceftaroline or ceftobiprole for community-acquired pneumonia; linezolid alone or plus fosfomycin for infection-related ventilator-associated complications or for central nervous system infections; daptomycin alone or plus clindamycin for necrotizing skin and soft tissue infections. (4) Conclusions: We are confident that targeted therapies based on scientific evidence and optimization of the pharmacokinetic/pharmacodynamic features of antibiotic monotherapy or combo therapy may represent valuable strategies for treating MSSA and MRSA infections.
1. Introduction
Staphylococcus aureus represents one of the major causes of infection among critically ill patients, with a remarkable burden of morbidity and mortality [1,2]. A recent study conducted among 15,202 critically ill patients admitted to 1150 different intensive care units (ICUs) found that 37.0% of clinical isolates retrieved from cultures were Gram-positives, of which S. aureus represented more than 50% [3].
Resistance rates of S. aureus in Europe is progressively increasing, and currently the proportion of isolates resistant to methicillin (MRSA) is higher than 15% [4]. Additionally, a worrisome finding of the recent pandemic was the remarkable prevalence of documented S. aureus superinfections, mainly bloodstream infections (BSIs) and ventilator-associated pneumonia (VAP), that occurred among critically ill patients with COVID-19 [5,6].
ICU patients with S. aureus disease can be broadly split into two major categories: on the one hand, those admitted to the ICU because of primary invasive S. aureus infection (namely bacteremia, pneumonia, toxic shock syndrome, and severe necrotizing skin and soft-tissue infections), and on the other hand, those with the onset of hospital-associated S. aureus infections during the ICU stay, as it may occur typically because of >48 h of ICU stay, recent surgery, and/or implantation of intravascular devices [7]. Sometimes S. aureus may produce biofilm, namely a structurally complex extracellular polymeric matrix within which it may embed, and this may render microbiological eradication extremely challenging [2,7]. However, this feature is a common occurrence in chronic infections (i.e., osteomyelitis and orthopedic prosthetic-associated infections), which are rarely encountered in the ICU scenario [2].
Early and prompt anti-MRSA therapy has become a standard approach to face suspected staphylococcal infections in the ICU patients [8]. Dedicated bundles for the treatment of BSIs caused by S. aureus were shown to be associated with favorable impact on survival rate [9]. The positive impact of bundles could be furtherly increased if antimicrobial selection were based also on some pharmacokinetic/pharmacodynamic (PK/PD) features, namely the penetration rate and the probability of optimal PK/PD target attainment at the infection site [10]. Rapid diagnostic tests, by providing real-time identification of the pathogen and of resistance markers, could be of further benefit [10,11,12].
In this regard, the establishment of a coordinated multidisciplinary task force, composed of the intensive care physician, the infectious disease consultant, the clinical microbiologist, and the MD clinical pharmacologist, could represent an innovative team focused on maximizing antibiotic efficacy, reducing overconsumption, and minimizing the development of antimicrobial resistance in the ICU setting [9,13].
The aim of this multidisciplinary opinion article was to develop algorithms for targeted antibiotic therapy of infections caused by methicillin susceptible S. aureus (MSSA) and MRSA in critically ill patients. The objective was to provide a useful guidance for clinicians in selecting treatment options based on scientific evidence, PK/PD properties of antimicrobials and site of infection.
2. Materials and Methods
A multidisciplinary team, composed of one intensive care physician (B.V.), one infectious disease consultant (P.V.), one clinical microbiologist (G.M.R.), and one MD clinical pharmacologist (F.P.), had several virtual meetings for developing algorithms for targeted antimicrobial therapy of severe MSSA and MRSA infections. Algorithms were organized for different sites of infection (namely infective endocarditis [IE], primary bloodstream infections [BSIs], infections associated with intracardiac/intravascular devices, community-acquired pneumonia [CAP], infection-related ventilator-associated complications (IVACs), central nervous system [CNS] infections, and necrotizing skin and soft tissue infections), and therapeutic strategies were based also on PK/PD features [10,14]. A researcher (M.G.) retrieved the scientific evidence for supporting the specific proposals by means of a PubMed-MEDLINE literature search (until August 2022). Key terms concerning selected antibiotics, genotype of resistance and/or antibiotic susceptibility pattern of S. aureus, and site of infections were searched in combination. The searched terms were oxacillin, cefazolin, daptomycin, fosfomycin, ceftobiprole, ceftaroline, vancomycin, teicoplanin, linezolid, methicillin-susceptible Staphylococcus aureus, methicillin-resistant Staphylococcus aureus, MRSA, MSSA, bloodstream infections, bacteremia, infective endocarditis, cardiac implantable electronic device infections, community-acquired pneumonia, hospital-acquired pneumonia, nosocomial pneumonia, pneumonia, ventilator-associated pneumonia, infection-related ventilator-associated complications, central nervous system infections, ventriculitis, meningitis, complicated skin and soft tissue infections, necrotizing soft tissue infections, necrotizing fasciitis, intensive care unit, and critically ill patients. Quality of evidence was established according to a hierarchical scale of the study design, as reported in the evidence pyramid [15]: randomized controlled trials (RCTs), prospective observational studies, retrospective observational studies, case series, case reports, and in vivo/in vitro preclinical studies. International guidelines/guidance documents issued by the Infectious Disease Society of America and/or by the European Society of Clinical Microbiology and Infectious Diseases, systematic reviews, and meta-analyses were also consulted. Consistence between retrieved studies was also considered by assessing the concordance in clinical outcome of the included studies at each level of the evidence pyramid. Only articles published in the English language were considered, with a main focus on those published in the last ten years.
Agreement between all of the four team members was reached on each of the options provided in the therapeutic algorithms after thoroughly discussion based on specific long-standing experience and expertise of each single member.
3. Targeted Treatment of Infections Caused by Staphylococcus aureus in Critically Ill Patients
Two targeted treatment algorithms were developed, one for MSSA infections and the other for MRSA infections, respectively.
3.1. Targeted Treatment of MSSA Infections
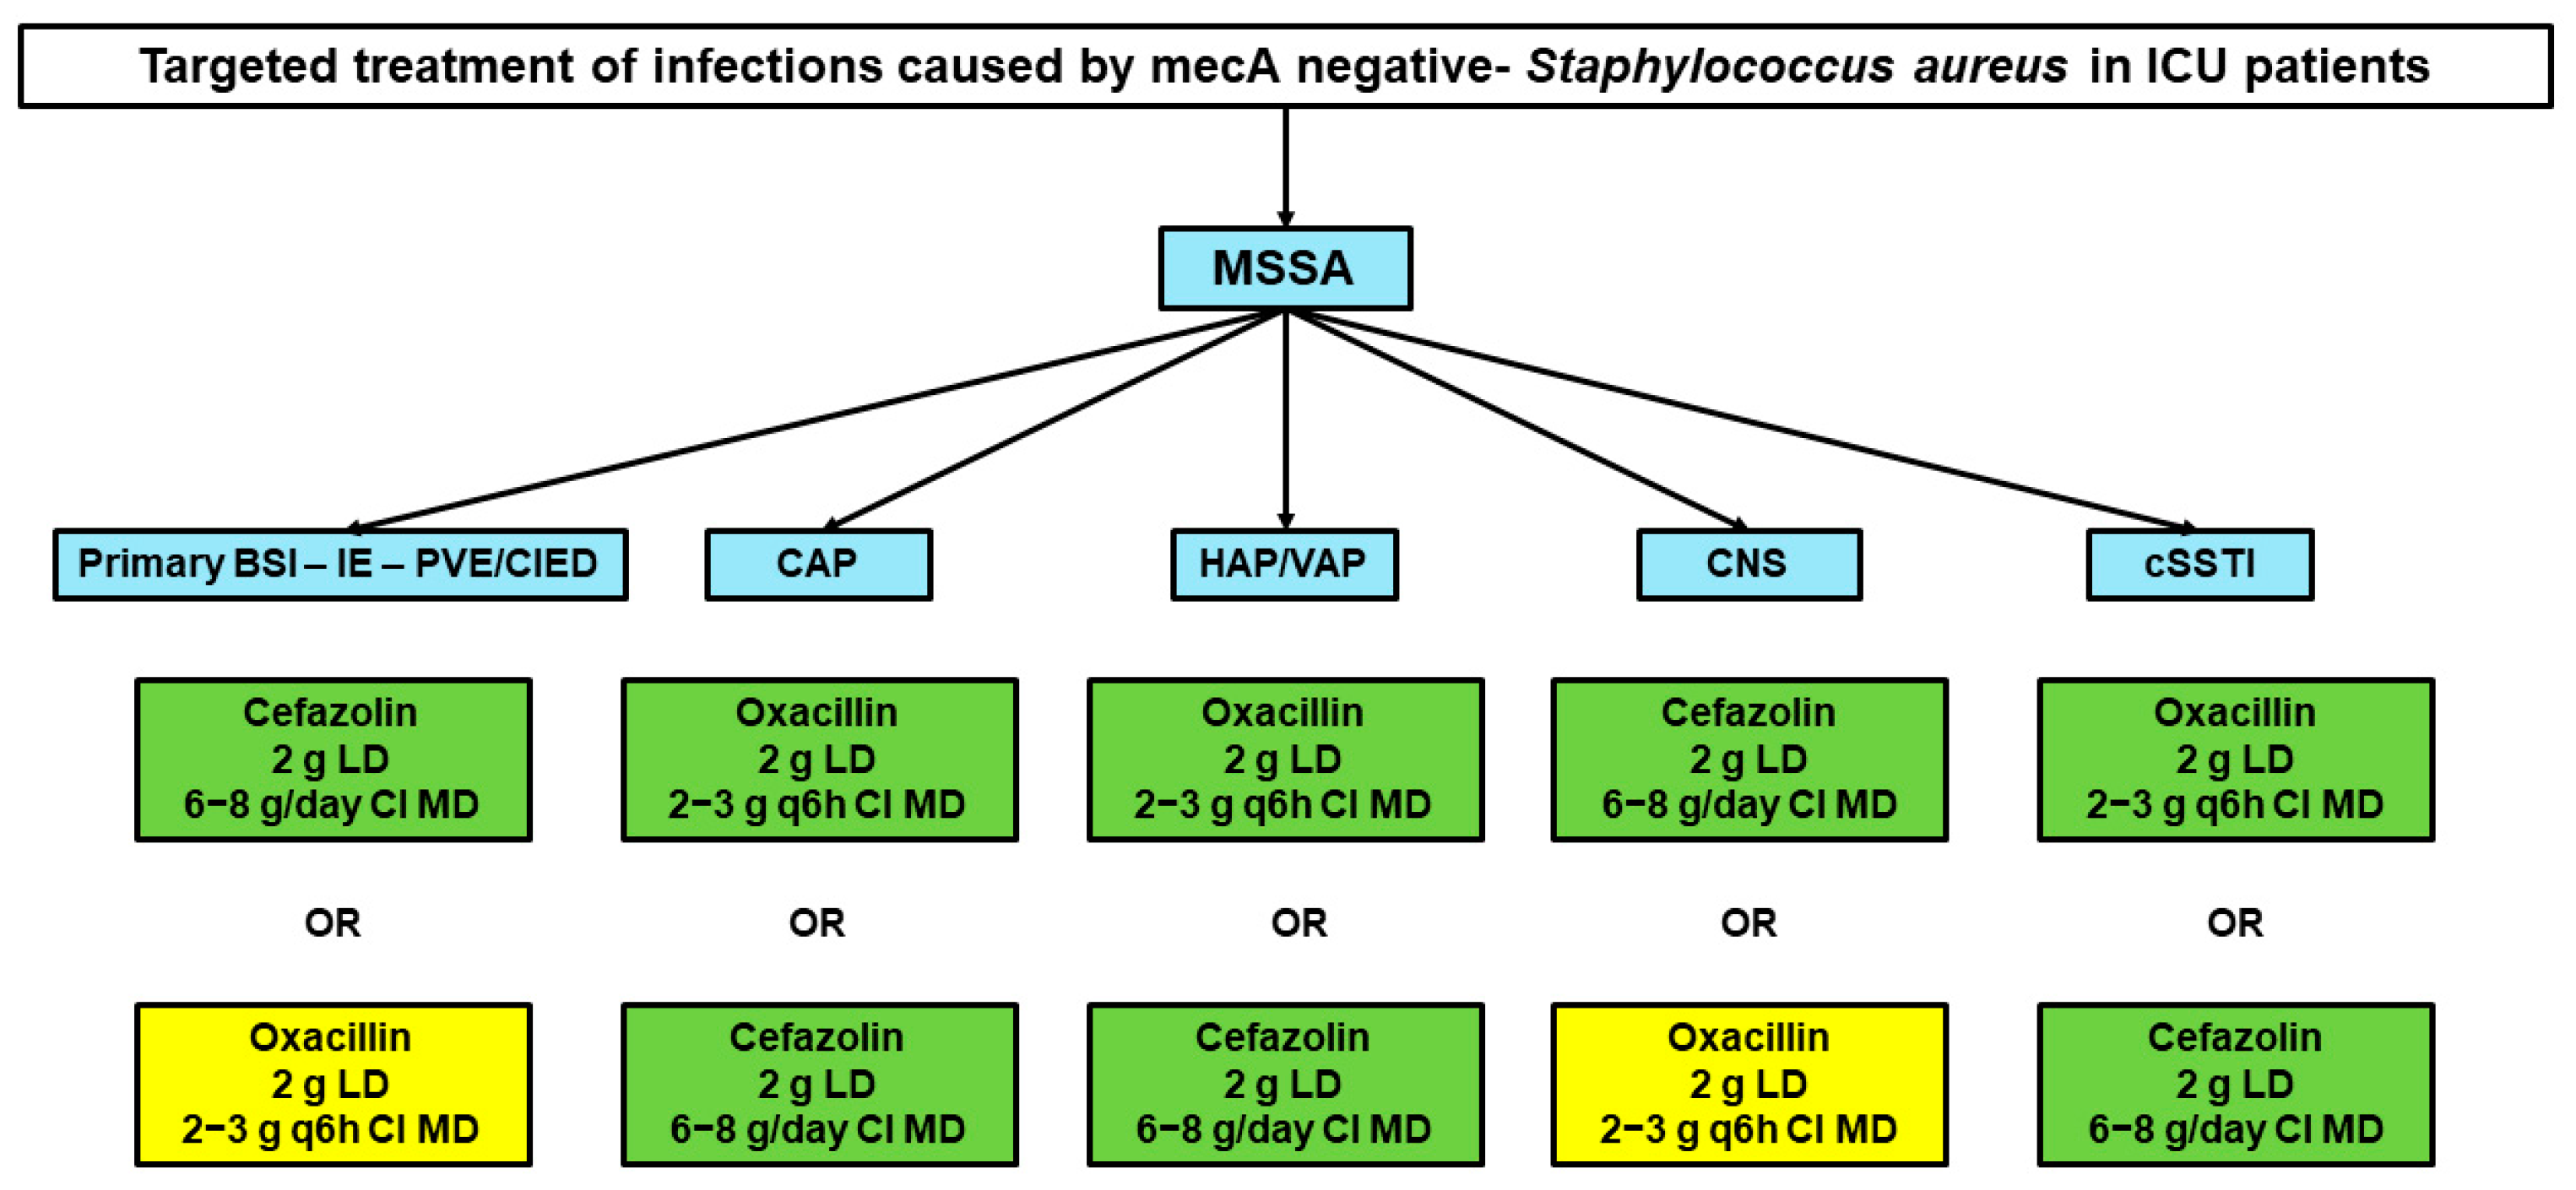
Oxacillin (2–3 g q6 h over 6 h by continuous infusion [CI] after 2 g loading dose [LD]) or cefazolin (2 g LD followed by 6–8 g/day by CI) are suggested as targeted therapy for the management of all types of infection caused by MSSA in critically ill patients. The types of infection taken into account were primary or catheter-related BSI, IE, infections associated with intracardiac devices, CAP, IVACs, CNS infections, and necrotizing fasciitis (Figure 1). The scientific evidence supporting these choices was summarized in Table 1.
Figure 1.
Algorithms for targeted therapy of infections caused by methicillin-susceptible Staphylococcus aureus. Green box: best therapeutic regimen according to current evidence; yellow box: alternative therapeutic regimen according to current evidence. BSI: bloodstream infection; CAP: community-acquired pneumonia; CI: continuous infusion; CIED: cardiac implantable electronic device infections; CNS: central nervous system; cSSTI: complicated skin and soft tissue infection; HAP: hospital-acquired pneumonia; ICU: intensive care unit; IE: infective endocarditis; LD: loading dose; MD: maintenance dose; PVE: prosthetic valve endocarditis; VAP: ventilator-associated pneumonia.
Table 1.
Summary of studies investigating the treatment of different types of infection caused by methicillin-susceptible Staphylococcus aureus with oxacillin or cefazolin.
In regard to BSI, a recent meta-analysis of ten observational studies compared the efficacy of cefazolin and oxacillin in the management of primary and secondary BSIs (34% skin and soft tissue infections, 27% IEs, and 18% pneumonia) caused by MSSA [16]. Cefazolin was significantly associated with lower mortality rate (RR 0.78; 95%CI 0.69–0.88), higher clinical cure rate (RR 1.09; 95%CI 1.02–1.17), and lower risk of drug withdrawal for adverse events (AEs; RR 0.27; 95%CI 0.16–0.47) compared to oxacillin [16]. Conversely, no difference in the relapse rate of BSIs was found between cefazolin and oxacillin treatment (RR 1.29; 95%CI 0.96–1.74). These findings were confirmed in a large multicentric retrospective study that included 3167 patients affected by primary or secondary MSSA BSIs (ICU admission 17.6%) [17]. In that study, cefazolin showed a significantly lower mortality rate both at 30-day (aHR 0.63; 95%CI 0.51–0.78) and at 90-day (aHR 0.77; 95%CI 0.66–0.90) compared to oxacillin or nafcillin. No difference in the relapse rate of BSI was found between the two therapeutic regimens (aOR 1.13; 95%CI 0.94–1.36). Conversely, a recent large multicentric retrospective study including 7312 patients with MSSA BSIs (ICU admission 13.5%) showed no difference in the 30-day mortality rate between cefazolin and flucloxacillin at propensity adjusted analysis (aOR 0.86; 95%CI 0.65–1.14) [18]. Likewise, no difference between cefazolin and antistaphylococcal penicillins (ASPs) was documented in several retrospective observational studies (ICU admission ranging from 5.2% to 41.8%) in terms of mortality rate, clinical cure rate, and relapse or recurrence rate of MSSA BSIs [19,20,21,22,23]. In a multicentric retrospective cohort study including 93 patients with complicated MSSA BSIs (41% related to bone and joint infections and 20% IE) [24], cefazolin showed a significantly lower clinical failure rate at 90-day (24% vs. 47%; p = 0.04) and AE rate (3% vs. 30%; p < 0.001) compared to oxacillin.
In regard to CNS infections, it should be mentioned that a study carried out among 17 patients with CNS infections caused by MS staphylococcal isolates showed that the percentage of cerebrospinal fluid (CSF) penetration could be higher for cefazolin than for cloxacillin (4.3% vs. 1.8%) [25].
Overall, oxacillin and cefazolin could be considered equivalent for the management of MSSA infections. Several real-world studies showed no significant difference between the two agents in terms of mortality, clinical cure, microbiological eradication, and relapse rate. However, cefazolin could provide some advantages in case of primary and/or secondary BSIs or CNS infections. In regard to the drug administration mode, it is worth mentioning that a retrospective cohort study including 107 patients with MSSA IE found that administration by CI was the only independent variable associated with 30-day microbiological cure with oxacillin at multivariate analysis (p = 0.01) and that CI granted significantly higher microbiological cure rate compared to intermittent infusion (94% vs. 79%; p = 0.03) [26]. These findings could support the use of CI for maximizing the achievement of optimal PK/PD with oxacillin. Notably, combination therapy did not add any advantage over cefazolin or oxacillin monotherapy in the management of MSSA infections. A recent meta-analysis of 12 studies found that combination therapy did not reduce significantly the mortality rate at day 30 (RR 0.92; 95%CI 0.70–1.20), at day 90 (RR 0.89; 95%CI 0.74–1.06), or at any time (RR 0.91; 95%CI 0.76–1.08) in the treatment of MSSA bacteremia compared to monotherapy [27]. Furthermore, combination therapy was associated with a significantly higher risk of AEs (including nephrotoxicity) (RR 1.74; 95%CI 1.31–2.31; p < 0.001). Additionally, a retrospective observational study including 350 patients with MSSA bacteremia (ICU admission 19.5%) found that combination therapy of daptomycin with a beta-lactam failed in reducing mortality rate compared to beta-lactam monotherapy after propensity score-matched analysis (90-day mortality rate: HR 0.89; 95%CI 0.54–1.49) [28].
3.2. Targeted Treatment of MRSA Infections
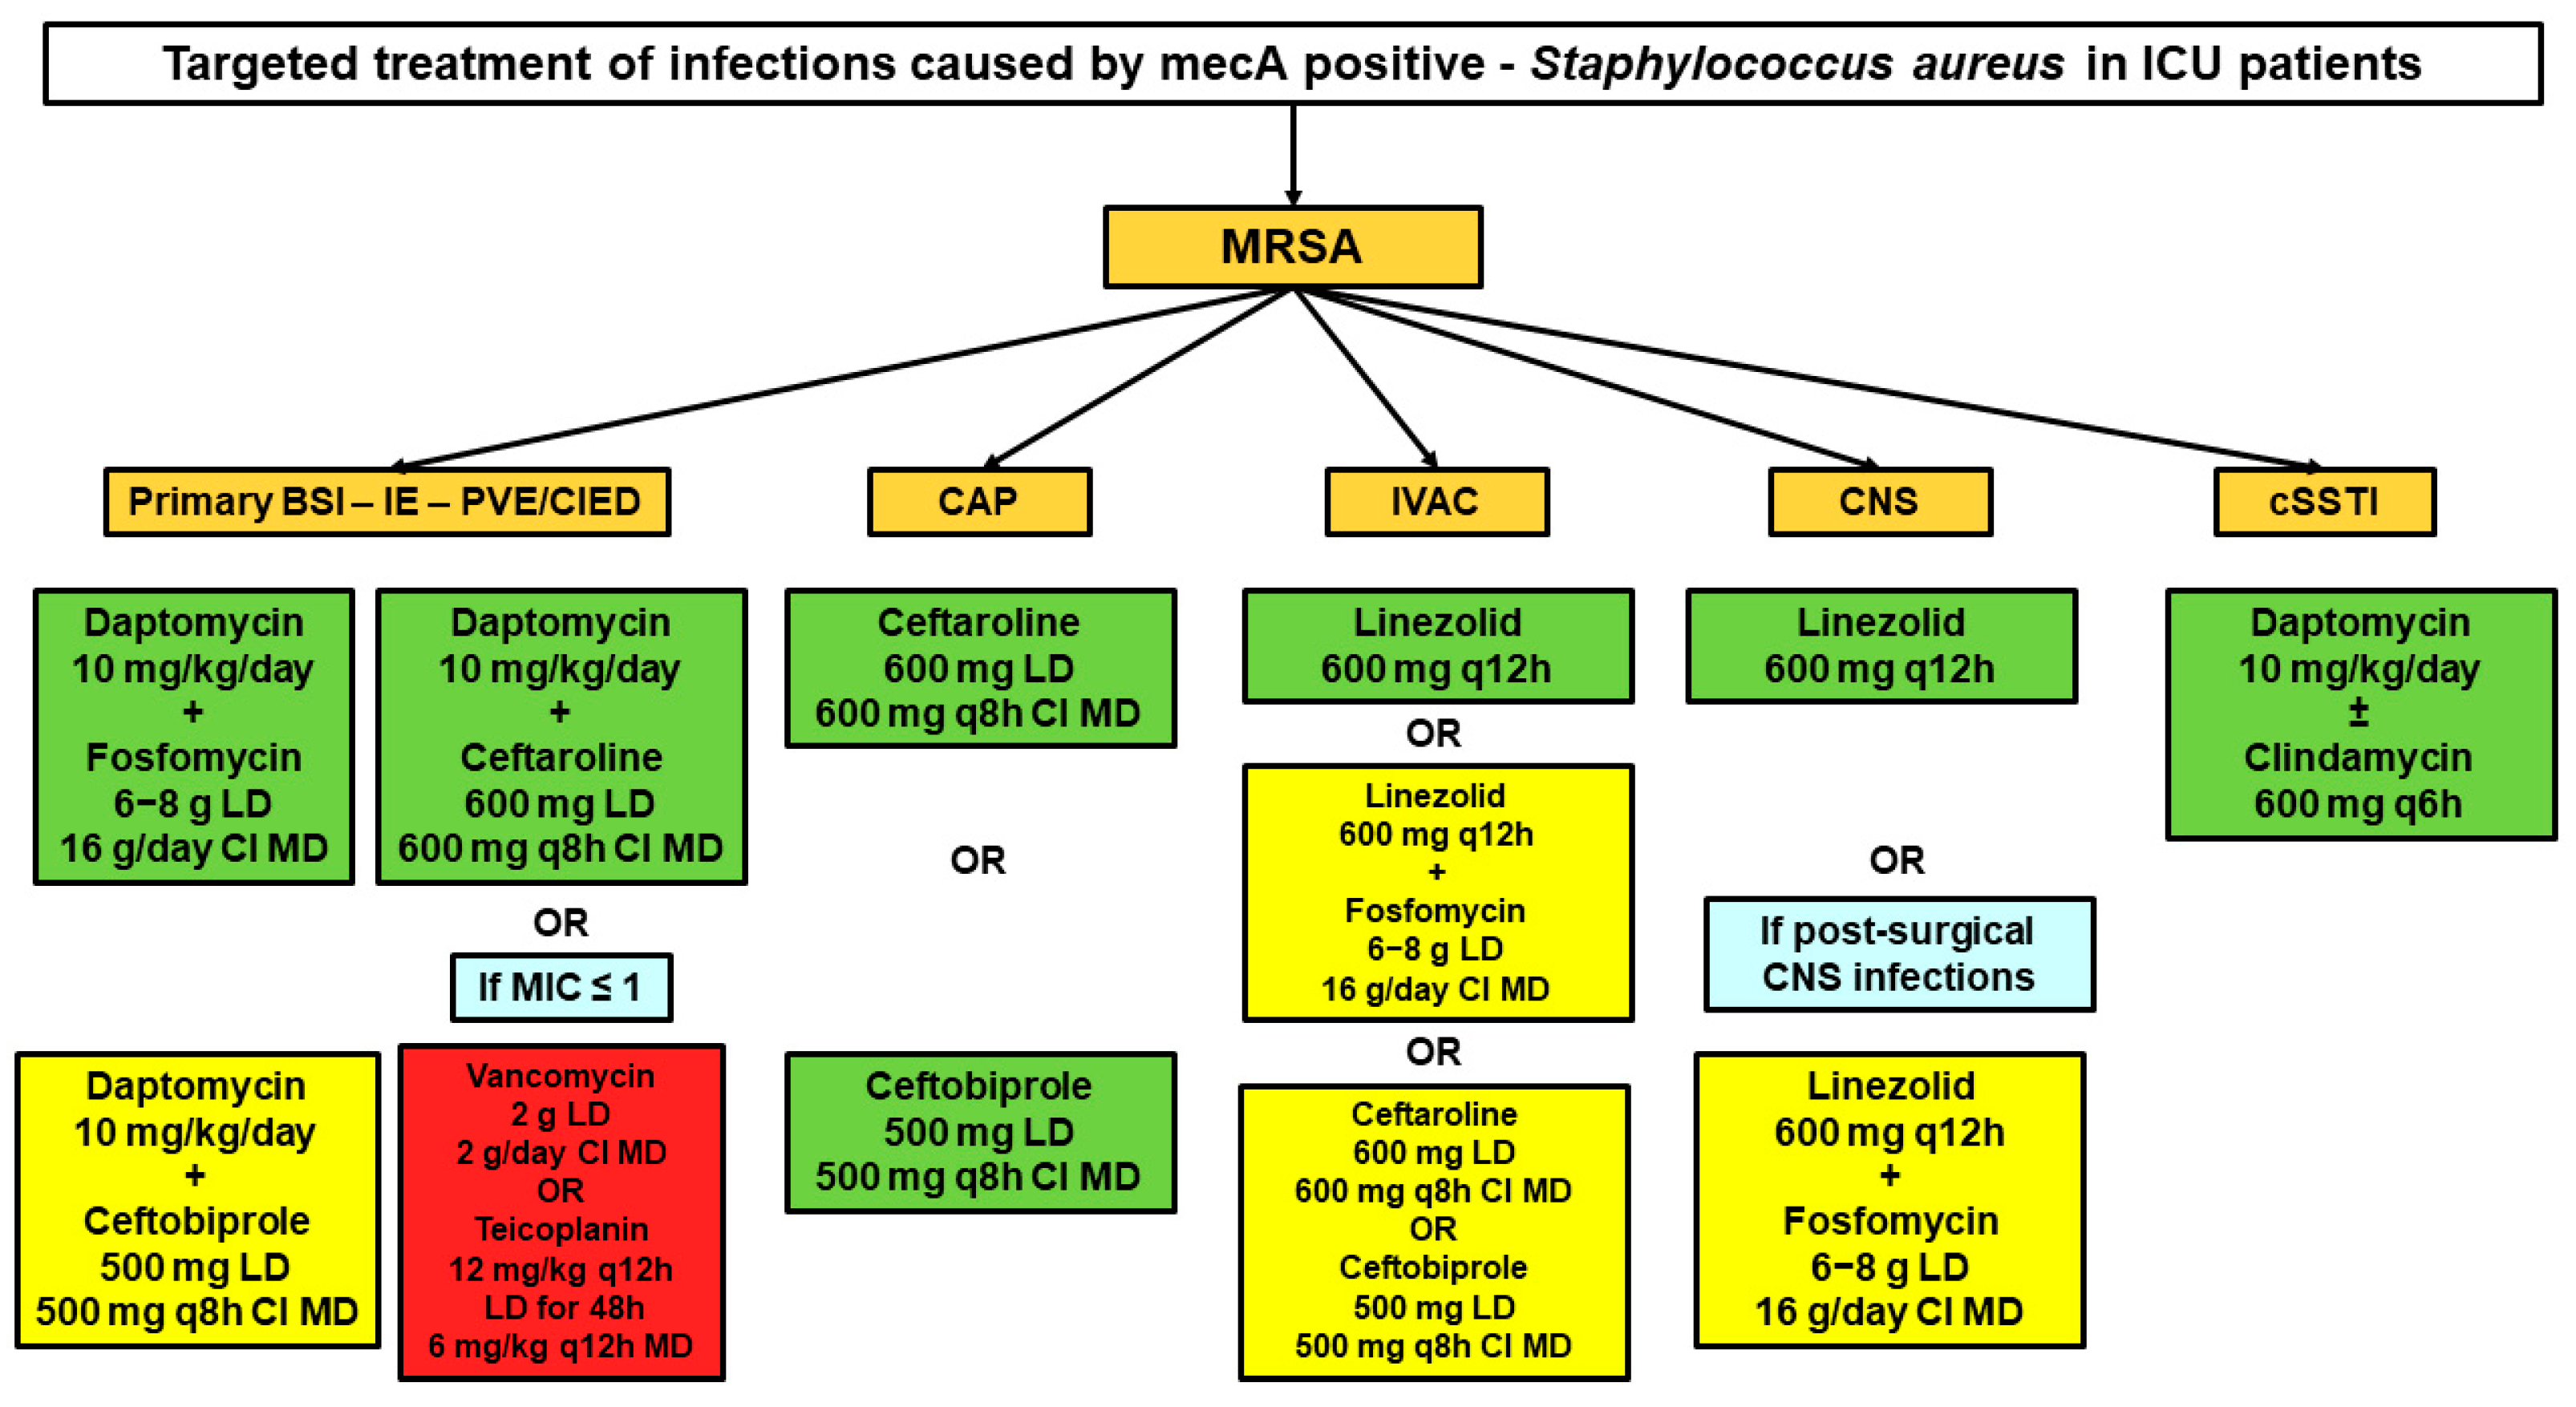
The therapeutic algorithm for targeted treatment of infections caused by MRSA in critically ill patients was organized according to the types of infection site and is shown in Figure 2. The scientific evidence supporting the different choices is summarized in Table 2.
Figure 2.
Algorithms for targeted therapy of BSIs or IE caused by methicillin-resistant Staphylococcus aureus. Green box: best therapeutic regimen according to current evidence; yellow box: alternative therapeutic regimen according to current evidence; red box: therapeutic regimen recommended only in specific situations. BSI: bloodstream infection; CAP: community-acquired pneumonia; CI: continuous infusion; CIED: cardiac implantable electronic device infections; CNS: central nervous system; cSSTI: complicated skin and soft tissue infection; ICU: intensive care unit; IE: infective endocarditis; IVAC: infective ventilator-associated complications; LD: loading dose; MD: maintenance dose; PVE: prosthetic valve endocarditis.
Table 2.
Summary of studies investigating the treatment of infection caused by methicillin-resistant Staphylococcus aureus according to the different sites of infection.
3.2.1. Primary BSIs, Infective Endocarditis, and Intracardiac/Intravascular Devices Infections
Combination therapy with high-dose daptomycin (10 mg/kg q24 h) plus CI fosfomycin (16 g/day after 6–8 g LD) or an anti-MRSA cephalosporin (ceftaroline 600 mg q8 h over 8 h after 600 mg LD or ceftobiprole 500 mg q8 h over 8 h after 500 mg LD) is suggested as first-line targeted therapy of primary BSIs (including catheter related), IEs, or infections associated with intracardiac/intravascular devices caused by MRSA. Vancomycin (2 g/day by CI after 2 g LD) or teicoplanin (6 mg/kg q12 h after an LD of 12 mg/kg q12 h for 4–5 doses) should be reserved as second line alternatives and could be suitable whenever vancomycin MIC is ≤1 mg/L (Figure 2).
In a recent RCT [29], 155 patients with MRSA BSI were randomized to receive daptomycin in monotherapy or in combination therapy with fosfomycin. Combination therapy granted significantly lower rates of both complicated BSI (16.2% vs. 32.1%; p = 0.022) and 6-week microbiological failure (0% vs. 11.1%; p = 0.003) compared to monotherapy. Additionally, in patients receiving combination therapy a trend toward higher treatment success rate at 6-week was found (54.1% vs. 42.0%; p = 0.14). Conversely, combination therapy was associated with significantly higher AE rate (17.6% vs. 4.9%; p = 0.018). In the subgroup analysis of patients with Pitt score > 1, a significantly higher cure rate was observed with combination therapy compared to monotherapy (57.1% vs. 22.7%; p = 0.023). This is in agreement with the findings of an early case series of three patients with staphylococcal IEs, one of whom had prosthetic valve endocarditis (PVE), who were successfully treated with daptomycin plus fosfomycin [30].
In regard to preclinical models, a rabbit model of experimental MRSA endocarditis investigated the efficacy of daptomycin plus fosfomycin vs. daptomycin alone and showed that combo therapy granted significantly better efficacy in terms of both proportion of sterile vegetations (100% versus 72%; p = 0.046) and bacterial burden reduction within the vegetations (p = 0.025) [31].
Several clinical studies may support the efficacy of combining daptomycin with ceftaroline in the management of MRSA BSIs, IE, or PVE [32,33,34,35,36,37,38,39,40,41]. An RCT including 40 patients randomized to combination therapy with daptomycin plus ceftaroline or to daptomycin/vancomycin monotherapy of MRSA BSIs (ICU admission up to 18%) showed that combination therapy was associated with significantly lower in-hospital mortality rate (0% vs. 26%; p = 0.029) [32]. The surprising findings led the investigators to stop early the study due to an unacceptable higher risk of mortality in the monotherapy arm. Conversely, two large retrospective studies found no difference in terms of mortality rate, hospital readmission, and BSI recurrence of combination therapy with daptomycin plus ceftaroline vs. standard of care monotherapy with vancomycin, daptomycin, or ceftaroline in the treatment of MRSA BSI [33,34]. However, in a subgroup of patients with severe disease (median Charlson Comorbidity Index ≥ 3) and with a primary endovascular source of infection, treatment with daptomycin plus ceftaroline within 72 h from index cultures resulted in a trend toward reduced mortality rate (4.3% vs. 20.8%; p = 0.16) [33]. A retrospective cohort study compared combination of daptomycin plus ceftaroline vs. standard of care with daptomycin or vancomycin plus gentamycin or rifampicin in the treatment of complicated MRSA BSI (ICU admission up to 57%) [35]. Combo therapy with daptomycin plus ceftaroline was associated with 77% lower odds of clinical failure at multivariate analysis (OR 0.23; 95%CI 0.06–0.89) and with a significantly lower risk of 60-day recurrence (0% vs. 30%; p < 0.01). Cunha et al. reported one case of MRSA aortic PVE successfully treated with a 6-week combination therapy course of high-dose daptomycin (i.e., 12 mg/kg/day) plus ceftaroline [41].
Real-world clinical evidence supporting the use of combination therapy with daptomycin plus ceftobiprole for MRSA BSIs and/or IE is limited only to one case series and one single case report [42,43]. In a case series of 12 staphylococcal IE (of which two-thirds were PVE) treated with ceftobiprole (5/12 underwent surgical intervention because of vegetation size or severe valve dysfunction with heart failure), 11/12 were treated with ceftobiprole plus daptomycin with a clinical cure rate of 83% and none with BSI relapse [42]. Interestingly, an in vitro study assessing the synergic activity of four different antibiotic combinations against 20 MRSA strains found that combo of ceftobiprole plus daptomycin was always synergic against all of the evaluated strains with a four-fold MIC decrease [44].
In regard to glycopeptides, a large multicenter retrospective study assessed 7411 patients with MRSA BSIs treated with vancomycin (n = 6805) or with vancomycin switched to daptomycin (n = 606) during the first hospitalization (108 in the first three days) [45]. MIC for vancomycin was >1 mg/L in 8.2–16.0% of isolates. The overall 30-day mortality rate did not differ between the two groups (aHR 0.87; 95%CI 0.69–1.09) but resulted significantly lower in the subgroup of patients having early switch to daptomycin (aHR 0.48; 95%CI 0.25–0.92). A recent RCT randomized 352 patients with MRSA BSIs to daptomycin/vancomycin monotherapy or daptomycin/vancomycin combined with an anti-staphylococcal beta-lactam (oxacillin, cloxacillin, or cefazolin). No difference between groups was found in the primary composite outcome (90-day mortality rate, relapse, microbiological failure rate, or persistent BSI) (mean difference −4.2%; 95%CI −14.3–6%), but patients receiving combination therapy had significantly higher risk of acute kidney injury (23% vs. 6%; p < 0.001) [46].
Overall, combination therapy with daptomycin plus fosfomycin or ceftaroline/ceftobiprole could be the preferred therapeutic strategy for the management of BSIs, IEs and/or infections associated with intracardiac/intravascular devices caused by MRSA. These combinations could grant lower risk of both clinical/microbiological failure and recurrence compared to monotherapy. In regard to PVE, a recent meta-analysis of four studies found no benefits of either gentamicin (OR 0.98; 95%CI 0.39–2.46) or rifampicin (OR 1.29; 95%CI 0.71–2.33) addition in reducing clinical failure in the treatment of staphylococcal PVE [47]. Conversely, the unfavorable PK/PD profile coupled with the safety issues should limit the role of glycopeptides in the treatment critically ill patients with MRSA BSIs, IEs, and/or infections associated with intracardiac/intravascular devices.
3.2.2. Community-Acquired Pneumonia
CI ceftaroline (600 mg q8 h over 8 h after 600 mg LD) or CI ceftobiprole (500 mg q8 h over 8 h after 500 mg LD) are suggested as first-line therapy of severe CAP in patients with risk factors or clinical/radiological features evocative for MRSA etiology (Figure 2).
A recent meta-analysis of 14 studies in patients with pneumonia (of which five were retrospective and provided data on clinical outcome in 345 patients with documented MRSA pneumonia) reported that the pooled success rate of ceftaroline was of 71.7% (95%CI: 59.7–82.3) [48]. A retrospective cohort study including 89 patients affected by severe CAP (10.1% due to MRSA; ICU admission 37%) treated with ceftaroline found a clinical failure rate of 36% [49]. Interestingly, the only independent predictor of clinical failure was the time elapsed from the diagnosis of severe CAP and the start of treatment with ceftaroline (OR for each passing day 1.5; 95%CI 1.1–1.9; p = 0.003) [49].
One RCT [50] and one retrospective observational study [51] may support the use of ceftobiprole for severe MRSA CAP. A phase III RCT [50] randomized 638 patients with CAP (4% bacteraemic; 2% MRSA) to ceftobiprole or ceftriaxone plus linezolid. No significant difference between the two groups was found in terms of overall clinical cure rate (86.6% vs. 87.4%) and/or microbiological eradication rate (88.2% vs. 90.8%). A retrospective cohort study [51] including 29 patients treated with ceftobiprole (19.3% CAP; septic shock 13.8%), of whom 24% were affected by MRSA pneumonia, found a clinical cure rate of 68.9% (66.7% in the subgroup of patients affected by CAP). No clinical failure occurred in the subgroup of patients affected by MRSA pneumonia.
Overall, ceftaroline and ceftobiprole could be reasonable options for the treatment of severe MRSA CAP in critically ill patients. Both agents showed similar penetration rate in the epithelial lining fluid (ELF) (20–25%) [52,53]. In regard to mode of administration, some studies suggested that in the treatment of critically ill patients, CI may allow the attainment of higher PK/PD targets with ceftaroline against MRSA compared to intermittent infusion [54,55]. Likewise, the same could be anticipated for ceftobiprole, even if real-world evidence is currently lacking.
3.2.3. Infection-Related Ventilator-Associated Complications
Linezolid (600 mg q12 h) in monotherapy or in combination therapy with CI fosfomycin (16 g q24 h after 6–8 g LD) is suggested as first-line targeted therapy of IVACs caused by MRSA. CI ceftaroline (600 mg q8 h over 8 h after 600 mg LD) or CI ceftobiprole (500 mg q8 h over 8 h after 500 mg LD) could be suggested as potential alternatives, especially in case of bacteraemic infections [56] (Figure 2).
Two meta-analyses [57,58] may support the use of linezolid for treating IVACs due to MRSA. In the first one, Kato et al. [57] analyzed seven RCTs and eight retrospective cohort and/or case-control studies comparing linezolid and vancomycin for the treatment of hospital-acquired or ventilator-associated pneumonia caused by MRSA. Clinical cure and microbiological eradication rates were significantly increased in patients treated with linezolid in both the RCTs (clinical cure: RR 0.81; 95%CI 0.71–0.92; microbiological eradication: RR 0.71; 95%CI 0.62–0.81) and the retrospective studies (clinical cure: OR 0.35; 95%CI 0.18–0.69). Mortality rates were comparable between the two groups in both the RCTs (RR 1.08; 95%CI 0.88–1.32) and the retrospective studies (OR 1.20; 95%CI 0.94–1.53), and no significant difference emerged in terms of AEs. In the second one, Jiang et al. included 12 RCTs comparing linezolid with glycopeptides for the treatment of nosocomial pneumonia [58]. Linezolid was associated with better microbiological eradication rate compared to glycopeptides (RR 1.16; 95%CI 1.03–1.31; p = 0.01), whereas no statistically significant difference was found in terms of either clinical cure rate (RR 1.08; 95%CI 1.00–1.17; p = 0.06) or all-cause mortality (RR 0.95; 95%CI 0.83–1.09; p = 0.46) between the two groups. A higher risk of rash (RR 0.41; 95%CI 0.24–0.71; p = 0.001) and nephrotoxicity (RR 0.41; 95%CI 0.27–0.64; p < 0.0001) was observed with glycopeptides.
Only preclinical studies may support the role of combining fosfomycin with linezolid for the treatment of MRSA infections [59,60,61,62,63]. A systematic review of seven in vitro preclinical studies documented a synergic effect between linezolid and fosfomycin against 95% of 166 Staphylococcus aureus strains, regardless of being planktonic or embedded within the biofilm [59]. In the same review, two in vivo preclinical studies were reported to grant higher efficacy when linezolid was combined with fosfomycin compared to each single agent alone [59].
One meta-analysis [48] and one retrospective cohort study (CAPTURE) [64] may support the use of ceftaroline for the management of severe HAP due to MRSA, including IVACs. A recent meta-analysis of 14 studies in patients with pneumonia (of which five were retrospective and provided data on clinical outcome in 345 patients with documented MRSA pneumonia) reported that the pooled success rate of ceftaroline was 83.0% (95%CI: 65.0–95.0) in HAP/VAP and 71.7% (95%CI: 59.7–82.3) in MRSA pneumonia [48]. A retrospective cohort study including 40 patients affected by HAP/VAP treated with off-label ceftaroline (67.5% ICU admission) found that the clinical success rate was 75% overall (81% and 62% for HAP and VAP, respectively) and 58% in the MRSA subgroup [64].
One post hoc retrospective analysis of a phase III RCT [65], one retrospective cohort study [51], and one in vitro study [66] may support the use of ceftobiprole for severe hospital-acquired pneumonia (HAP) due to MRSA, including IVACs. A post hoc analysis of a phase III RCT including 307 high-risk patients with HAP found that early response (at day 4) was higher among ceftobiprole-treated patients than among comparator-treated patients (12.5% difference; 95%CI 3.5–21.4) [65]. A retrospective cohort study [51] including 29 patients treated with ceftobiprole (48.3% HAP, of which one case of IVAC; septic shock 13.8%), of which 24% were affected by MRSA pneumonia, found a clinical cure rate of 68.9% (85.7% in the subgroup of patients affected by HAP). No clinical failure occurred in the subgroup of patients with MRSA pneumonia. Among 66 MRSA isolates retrieved from HAP, 63/66 (95.5%) were susceptible to ceftobiprole (MIC50 1 mg/L; MIC90 2 mg/L), and 3/66 were ceftobiprole-resistant but with a borderline MIC of 4 mg/L [66].
Overall, linezolid could be considered the preferred therapeutic option for the management of IVACs caused by MRSA. Real-world evidence showed higher clinical cure rate and microbiological eradication rate compared to vancomycin. Linezolid showed very high penetration rate into the ELF of critically ventilated patients (97%), and this may grant effective PK/PD target attainment against MRSA with an MIC up to 2 mg/L [67,68,69]. Fosfomycin showed high penetration rate into the ELF of critically septic patients (>50%) [70] and may theoretically represent a valuable add-on for combo therapy with linezolid according to even physicochemical properties and synergic activity. Novel anti-staphylococcal cephalosporins could be a promising but second-line alternative for IVACs due to MRSA, considering that studies supporting the use of these agents in ICU scenario are limited (mainly assessed in CAP) compared to those available for linezolid. ELF penetration rates were quite limited (20–25%) [52,53], but CI administration may be suggested for maximizing PK/PD target attainment in ventilated critical care patients with normal and/or augmented renal clearance [55].
3.2.4. Central Nervous System Infections
Linezolid (600 mg q12 h) is suggested in monotherapy as targeted therapy of primitive CNS infections caused by MRSA (Figure 2) and in combination therapy with fosfomycin (16 g/day CI after 6–8 g LD) as targeted therapy of post-operative neurosurgical MRSA infections.
Three retrospective studies, two case series, and two case reports may support the use of linezolid for the management of CNS infections caused by MRSA [71,72,73,74,75,76,77,78]. In a retrospective cohort of 66 patients with MRSA CNS infections (78.8% bacteraemic), salvage therapy with linezolid after previous failure of glycopeptide treatment had good efficacy with an in-hospital mortality rate of 13.6% and a relapse rate of 16.7% [71]. Among 26 patients treated with linezolid for Staphylococcus aureus meningitis (81% post-operative), the clinical cure rate was 69%, and the microbiological eradication rate was 93% [72]. A retrospective case-control study including 17 patients with MRSA meningitis found significantly higher microbiological cure rate at 5-day among those receiving linezolid compared to those receiving vancomycin (77.8% vs. 25.0%; p = 0.044) [73].
Only preclinical studies may support the role of combining fosfomycin with linezolid in treating MRSA infections, as previously mentioned [59,60,61,62,63].
Overall, linezolid could be considered the preferred therapeutic option for the management of CNS infections caused by MRSA. Real-world evidence showed greater clinical cure rate and microbiological eradication rate compared to glycopeptides. Linezolid showed good penetration rate into the cerebrospinal fluid (CSF) of neurocritical patients (57%) [79] and is expected to attain optimal PK/PD targets at the infection site. High-dose fosfomycin (i.e., 24 g/day) may theoretically represent a valuable add-on for combination therapy with linezolid in case of post-operative neurosurgical MRSA infections thanks to a good CSF penetration rate (27%) and to the fact that CSF concentrations were shown to remain above the clinical breakpoint for MRSA during the overall treatment period [80].
3.2.5. Necrotizing Skin and Soft Tissue Infections
High-dose daptomycin in monotherapy (10 mg/kg q24 h) or in combination therapy with clindamycin (600 mg q6 h) is suggested as first-line targeted therapy of necrotizing skin and soft tissue infections caused by MRSA (Figure 2).
A recent meta-analysis of seven studies (907 patients) compared daptomycin and vancomycin in the treatment of bacteraemic MRSA infections and found that treatment success rate with daptomycin was significantly higher in intermediate-risk sources, of which 28–33% were soft tissue infections, (OR 4.40; 95%CI 2.06–9.40; p < 0.001) [81]. A large European registry including 6075 patients treated with daptomycin, of which 1927 had complicated skin and soft tissue infections (31.5% MRSA), reported an overall clinical success of 84.7% (87.0% in subgroup of patients with MRSA skin and soft tissue infections) [82]. Notably, daptomycin switch to due to previous clinical failure with other antibiotic therapy was reported in as high as 53.7% of patients [82].
A recent retrospective cohort study including 190 patients affected by necrotizing soft tissue infections of lower limbs found that clindamycin was associated with 2.92 times reduced odds of having an amputation when compared with their counterparts, including in adjusted analysis (p = 0.015) [83]. No significant difference in mortality rate between patients receiving clindamycin as part of their initial antibiotic regimen and those treated with comparators was reported (8.3% vs. 11.6%; p = 0.45) [83].
Interestingly, a retrospective case-control study [84] including 62 critically ill patients affected by necrotizing soft tissue infections (22.6% caused by Staphylococcus aureus) found that an intensive multidisciplinary management (including early surgical debridement followed by daily inspection of surgical wounds, close microbiological surveillance, and targeted antibiotic strategy including high-dose daptomycin for MRSA coupled with clindamycin plus anti-pseudomonal beta-lactam) was more effective than standard management (in which on-demand consultation with emergency surgeon and infectious disease specialist coupled with the use of vancomycin as targeted therapy for MRSA), allowing for earlier control of infection and faster reduction of multiple organ dysfunction (ΔSOFA −5.2 ± 3.5 pts. vs. −2.1 ± 3.0 pts.; p = 0.003). Additionally, significant lower 7-day (3.1% vs. 20.0%; p = 0.049) and ICU mortality rate (15.6% vs. 40.0%; p = 0.032) was found in patients receiving intensive multidisciplinary management.
Overall, high-dose daptomycin could be suggested as targeted therapy of severe necrotizing skin and soft tissue infections caused by MRSA. Real-world data reported better clinical outcome compared to vancomycin in bacteraemic cases. Daptomycin showed very high penetration rate (i.e., 70–100%) in soft tissues [85,86], and this could maximize PK/PD target attainment at the infection site.
4. Expert Opinion
S. aureus represents a leading cause of infection among critically ill patients [3], and the widespread diffusion of MRSA is especially worrisome [4]. Several diagnostic platforms based on molecular methods are currently available for rapid detection of S. aureus and associated mec genes responsible for the methicillin-resistant phenotype. These systems work with positive blood cultures or directly with some clinical specimens [87] and can be very useful to rapidly assess, with high sensitivity, the presence of MSSA or MRSA as causes of infection, significantly shortening the time to targeted therapy. However, these systems cannot detect resistances to anti-MRSA cephalosporins and to non-beta-lactam agents, which should be tested by conventional phenotypic susceptibility testing.
In this context, the adoption of criteria that may provide the best therapeutic strategy in each of the different challenging scenarios may be fundamental [10,88].
In regard to MSSA infections, CI oxacillin or CI cefazolin monotherapy may represent the best choice for the management of the different types of infection, as no real-world evidence currently support the role of combination therapy.
In regard to MRSA infections, therapeutic choices should be guided by the infection site. Current evidence suggests that combination of high-dose daptomycin plus fosfomycin or ceftaroline/ceftobiprole may have very high probability of favorable clinical outcome and/or microbiological outcome in the treatment of primary BSIs or IE [29,32] and may represent a promising option for the management of infections associated with intracardiac/intravascular devices, including PVE [89]. Conversely, neither gentamicin nor rifampicin were shown to add significant advantages in this scenario [47]. It should also be noticed that several preclinical studies showed synergic activity between daptomycin and fosfomycin or ceftaroline [59,90,91], but the progressive emergence of fosfomycin-resistant and/or ceftaroline-resistant MRSA strains is quite worrisome [92,93,94,95]. Vancomycin and teicoplanin may be potential alternatives but were not considered as preferred agents due to the unfavorable PK/PD features (low bactericidal effect, risk of nephrotoxicity) [96,97,98]. Linezolid may be the preferred option in the treatment of deep-seated MRSA infections similar to CNS infections and/or IVACs based on the high penetration rates into the CSF and/or the ELF and on the favorable PK/PD features and [67,68,79,99]. Ceftaroline or ceftobiprole could be suggested as potential second-line alternatives in MRSA IVACs, especially in case of bacteraemic infections, although no pivotal trials were conducted in ICU scenario and real-world evidence are limited. High-dose daptomycin could be preferred in the treatment of severe MRSA necrotizing skin and soft tissue infections [100], especially when the pathophysiological alterations commonly retrieved in this type of infection may affect optimal PK/PD target attainment [101].
It should be mentioned that in patients allergic to oxacillin and/or cefazolin, good alternative options for the treatment of MSSA infections may be daptomycin, linezolid, or glycopeptides.
In conclusion, we are confident that these algorithm-based strategies could be helpful in improving clinical outcome in the treatment of challenging scenarios of S. aureus infections.
5. Conclusions
In an era characterized by the widespread diffusion of MRSA, implementing a multidisciplinary task force for targeting therapy in critically ill patients has become a real need. Our approach is focused on mirroring antibiotic therapy and on optimizing PK/PD target attainment at the infection site. These strategies could be helpful either in improving clinical outcome or in minimizing resistance spread. Availability of rapid molecular diagnostic tests for prompt identification of the causative pathogens will be fundamental for implementing antimicrobial stewardship programs based on the proposed algorithms.
Author Contributions
Conceptualization, B.V., G.M.R., F.P. and P.V.; methodology, M.G.; data curation, M.G.; writing—original draft preparation, M.G.; writing—review and editing, B.V., G.M.R., F.P. and P.V. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Data Availability Statement
The data presented in this review are retrieved and summarized from the different publicly available included studies.
Conflicts of Interest
M.G. received personal fees from Angelini; B.V participated in advisory boards and in the speaker’s bureau for and received research contracts, contributions, and study events from Abbott, Accelerate Diagnostics, Ada, Alifax, Angelini, Becton Dickinson, Bellco, Biomerieux, Biotest, Cepheid, Correvio, Gilead, Menarini, MSD Italia, Nordic Pharma, Pfizer, Shionogi, and Thermo Fisher Scientific; G.M.R participated in advisory boards and the speaker’s bureau for and received research contracts, contributions, and travel grants from Accelerate, Angelini, Arrow, Beckman Biomedical Service, Coulter, Becton-Dickinson, bioMérieux, Cepheid, Hain Life Sciences, Menarini, Meridian, MSD, Nordic Pharma, Pfizer, Qiagen, Q-linea, Qpex, Quidel, Qvella, Roche, Seegene, Set-Lance, Shionogi, Symcel, ThermoFisher, VenatorX, and Zambon; F.P participated in the speaker’s bureau for Angelini, Basilea Pharmaceutica, Gilead, Hikma, Merck Sharp & Dohme, Nordic Pharma, Pfizer, and Sanofi Aventis and participated in the advisory board for Angelini, Basilea Pharmaceutica, Correvio, Gilead, Merck Sharp & Dohme, Nordic Pharma, Novartis, Pfizer, and Thermo-Fisher. P.V has served as a consultant for Biomerieux, Gilead, Merck Sharp & Dohme, Nabriva, Nordic Pharma, Pfizer, Thermo-Fisher, and Venatorx and received payment for serving on the speaker’s bureau for Correvio, Gilead, Merck Sharp & Dohme, Nordic Pharma, and Pfizer. The authors report no other conflicts of interest in this work.
References
- Khader, K.; Thomas, A.; Huskins, W.C.; Stevens, V.; Keegan, L.T.; Visnovsky, L.; Samore, M.H. Effectiveness of Contact Precautions to Prevent Transmission of Methicillin-Resistant Staphylococcus Aureus and Vancomycin-Resistant Enterococci in Intensive Care Units. Clin. Infect. Dis. 2021, 72, S42–S49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tong, S.Y.C.; Davis, J.S.; Eichenberger, E.; Holland, T.L.; Fowler, V.G. Staphylococcus Aureus Infections: Epidemiology, Pathophysiology, Clinical Manifestations, and Management. Clin. Microbiol. Rev. 2015, 28, 603–661. [Google Scholar] [CrossRef] [Scilit]
- Vincent, J.-L.; Sakr, Y.; Singer, M.; Martin-Loeches, I.; Machado, F.R.; Marshall, J.C.; Finfer, S.; Pelosi, P.; Brazzi, L.; Aditianingsih, D.; et al. Prevalence and Outcomes of Infection Among Patients in Intensive Care Units in 2017. JAMA 2020, 323, 1478–1487. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- European Centre for Disease Prevention and Control Antimicrobial Resistance in the EU/EEA (EARS-Net)—Annual Epidemiological Report for 2020. Available online: https://www.ecdc.europa.eu/en/publications-data/antimicrobial-resistance-eueea-ears-net-annual-epidemiological-report-2020 (accessed on 31 October 2022).
- Grasselli, G.; Scaravilli, V.; Mangioni, D.; Scudeller, L.; Alagna, L.; Bartoletti, M.; Bellani, G.; Biagioni, E.; Bonfanti, P.; Bottino, N.; et al. Hospital-Acquired Infections in Critically Ill Patients with COVID-19. Chest 2021, 160, 454–465. [Google Scholar] [CrossRef] [Scilit]
- De Pascale, G.; De Maio, F.; Carelli, S.; De Angelis, G.; Cacaci, M.; Montini, L.; Bello, G.; Cutuli, S.L.; Pintaudi, G.; Tanzarella, E.S.; et al. Staphylococcus Aureus Ventilator-Associated Pneumonia in Patients with COVID-19: Clinical Features and Potential Inference with Lung Dysbiosis. Crit. Care 2021, 25, 197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sampedro, G.R.; Bubeck Wardenburg, J. Staphylococcus Aureus in the Intensive Care Unit: Are These Golden Grapes Ripe for a New Approach? J. Infect. Dis. 2017, 215, S64–S70. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, C.; Bayer, A.; Cosgrove, S.E.; Daum, R.S.; Fridkin, S.K.; Gorwitz, R.J.; Kaplan, S.L.; Karchmer, A.W.; Levine, D.P.; Murray, B.E.; et al. Clinical Practice Guidelines by the Infectious Diseases Society of America for the Treatment of Methicillin-Resistant Staphylococcus Aureus Infections in Adults and Children. Clin. Infect. Dis. 2011, 52, e18–e55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- López-Cortés, L.E.; Del Toro, M.D.; Gálvez-Acebal, J.; Bereciartua-Bastarrica, E.; Fariñas, M.C.; Sanz-Franco, M.; Natera, C.; Corzo, J.E.; Lomas, J.M.; Pasquau, J.; et al. Impact of an Evidence-Based Bundle Intervention in the Quality-of-Care Management and Outcome of Staphylococcus Aureus Bacteremia. Clin. Infect. Dis. 2013, 57, 1225–1233. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pea, F.; Viale, P. Bench-to-Bedside Review: Appropriate Antibiotic Therapy in Severe Sepsis and Septic Shock--Does the Dose Matter? Crit. Care 2009, 13, 214. [Google Scholar] [CrossRef] [Scilit]
- Abdul-Aziz, M.H.; Alffenaar, J.-W.C.; Bassetti, M.; Bracht, H.; Dimopoulos, G.; Marriott, D.; Neely, M.N.; Paiva, J.-A.; Pea, F.; Sjovall, F.; et al. Antimicrobial Therapeutic Drug Monitoring in Critically Ill Adult Patients: A Position Paper. Intensive Care Med. 2020, 46, 1127–1153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Poole, S.; Clark, T.W. Rapid Syndromic Molecular Testing in Pneumonia: The Current Landscape and Future Potential. J. Infect. 2020, 80, 1–7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bartoletti, M.; Tedeschi, S.; Scudeller, L.; Pascale, R.; Rosselli Del Turco, E.; Trapani, F.; Tumietto, F.; Virgili, G.; Marconi, L.; Ianniruberto, S.; et al. Impact on Mortality of a Bundle for the Management of Enterococcal Bloodstream Infection. Open Forum Infect. Dis. 2019, 6, ofz473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gatti, M.; Barnini, S.; Guarracino, F.; Parisio, E.M.; Spinicci, M.; Viaggi, B.; D’Arienzo, S.; Forni, S.; Galano, A.; Gemmi, F. Orthopaedic Implant-Associated Staphylococcal Infections: A Critical Reappraisal of Unmet Clinical Needs Associated with the Implementation of the Best Antibiotic Choice. Antibiotics 2022, 11, 406. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Murad, M.H.; Asi, N.; Alsawas, M.; Alahdab, F. New Evidence Pyramid. Evid. Based Med. 2016, 21, 125–127. [Google Scholar] [CrossRef] [Scilit]
- Rindone, J.P.; Mellen, C.K. Meta-Analysis of Trials Comparing Cefazolin to Antistaphylococcal Penicillins in the Treatment of Methicillin-Sensitive Staphylococcus Aureus Bacteraemia. Br. J. Clin. Pharmacol. 2018, 84, 1258–1266. [Google Scholar] [CrossRef] [Scilit]
- McDanel, J.S.; Roghmann, M.-C.; Perencevich, E.N.; Ohl, M.E.; Goto, M.; Livorsi, D.J.; Jones, M.; Albertson, J.P.; Nair, R.; O’Shea, A.M.J.; et al. Comparative Effectiveness of Cefazolin Versus Nafcillin or Oxacillin for Treatment of Methicillin-Susceptible Staphylococcus Aureus Infections Complicated by Bacteremia: A Nationwide Cohort Study. Clin. Infect. Dis. 2017, 65, 100–106. [Google Scholar] [CrossRef] [Scilit]
- Davis, J.S.; Turnidge, J.; Tong, S. A Large Retrospective Cohort Study of Cefazolin Compared with Flucloxacillin for Methicillin-Susceptible Staphylococcus Aureus Bacteraemia. Int. J. Antimicrob. Agents 2018, 52, 297–300. [Google Scholar] [CrossRef] [Scilit]
- Beganovic, M.; Cusumano, J.A.; Lopes, V.; LaPlante, K.L.; Caffrey, A.R. Comparative Effectiveness of Exclusive Exposure to Nafcillin or Oxacillin, Cefazolin, Piperacillin/Tazobactam, and Fluoroquinolones Among a National Cohort of Veterans with Methicillin-Susceptible Staphylococcus Aureus Bloodstream Infection. Open Forum Infect. Dis. 2019, 6, ofz270. [Google Scholar] [CrossRef] [Scilit]
- Rao, S.N.; Rhodes, N.J.; Lee, B.J.; Scheetz, M.H.; Hanson, A.P.; Segreti, J.; Crank, C.W.; Wang, S.K. Treatment Outcomes with Cefazolin versus Oxacillin for Deep-Seated Methicillin-Susceptible Staphylococcus Aureus Bloodstream Infections. Antimicrob. Agents Chemother. 2015, 59, 5232–5238. [Google Scholar] [CrossRef] [Scilit]
- Bai, A.D.; Findlater, A.; Irfan, N.; Singhal, N.; Loeb, M. Cefazolin versus Cloxacillin as Definitive Antibiotic Therapy for Methicillin-Susceptible Staphylococcus Aureus Spinal Epidural Abscess: A Retrospective Cohort Study. Int. J. Antimicrob. Agents 2021, 58, 106429. [Google Scholar] [CrossRef] [Scilit]
- Corsini Campioli, C.; Go, J.R.; Abu Saleh, O.; Challener, D.; Yetmar, Z.; Osmon, D.R. Antistaphylococcal Penicillin vs Cefazolin for the Treatment of Methicillin-Susceptible Staphylococcus Aureus Spinal Epidural Abscesses. Open Forum Infect. Dis. 2021, 8, ofab071. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lefèvre, B.; Hoen, B.; Goehringer, F.; Sime, W.N.; Aissa, N.; Alauzet, C.; Jeanmaire, E.; Hénard, S.; Filippetti, L.; Selton-Suty, C.; et al. Antistaphylococcal Penicillins vs. Cefazolin in the Treatment of Methicillin-Susceptible Staphylococcus Aureus Infective Endocarditis: A Quasi-Experimental Monocentre Study. Eur. J. Clin. Microbiol. Infect. Dis. 2021, 40, 2605–2616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, J.; Echevarria, K.L.; Hughes, D.W.; Cadena, J.A.; Bowling, J.E.; Lewis, J.S. Comparison of Cefazolin versus Oxacillin for Treatment of Complicated Bacteremia Caused by Methicillin-Susceptible Staphylococcus Aureus. Antimicrob. Agents Chemother. 2014, 58, 5117–5124. [Google Scholar] [CrossRef] [Scilit]
- Le Turnier, P.; Gregoire, M.; Deslandes, G.; Lakhal, K.; Deschanvres, C.; Lecomte, R.; Talarmin, J.-P.; Dubée, V.; Bellouard, R.; Boutoille, D.; et al. Should We Reconsider Cefazolin for Treating Staphylococcal Meningitis? A Retrospective Analysis of Cefazolin and Cloxacillin Cerebrospinal Fluid Levels in Patients Treated for Staphylococcal Meningitis. Clin. Microbiol. Infect. 2020, 26, 1415.e1–1415.e4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hughes, D.W.; Frei, C.R.; Maxwell, P.R.; Green, K.; Patterson, J.E.; Crawford, G.E.; Lewis, J.S. Continuous versus Intermittent Infusion of Oxacillin for Treatment of Infective Endocarditis Caused by Methicillin-Susceptible Staphylococcus Aureus. Antimicrob. Agents Chemother. 2009, 53, 2014–2019. [Google Scholar] [CrossRef] [Scilit]
- Grillo, S.; Puig-Asensio, M.; Schweizer, M.L.; Cuervo, G.; Oriol, I.; Pujol, M.; Carratalà, J. The Effectiveness of Combination Therapy for Treating Methicillin-Susceptible Staphylococcus Aureus Bacteremia: A Systematic Literature Review and a Meta-Analysis. Microorganisms 2022, 10, 848. [Google Scholar] [CrossRef] [Scilit]
- Grillo, S.; Cuervo, G.; Carratalà, J.; Grau, I.; Pallarès, N.; Tebé, C.; Guillem Tió, L.; Murillo, O.; Ardanuy, C.; Domínguez, M.A.; et al. Impact of β-Lactam and Daptomycin Combination Therapy on Clinical Outcomes in Methicillin-Susceptible Staphylococcus Aureus Bacteremia: A Propensity Score-Matched Analysis. Clin. Infect. Dis. 2019, 69, 1480–1488. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pujol, M.; Miró, J.-M.; Shaw, E.; Aguado, J.-M.; San-Juan, R.; Puig-Asensio, M.; Pigrau, C.; Calbo, E.; Montejo, M.; Rodriguez-Álvarez, R.; et al. Daptomycin Plus Fosfomycin Versus Daptomycin Alone for Methicillin-Resistant Staphylococcus Aureus Bacteremia and Endocarditis: A Randomized Clinical Trial. Clin. Infect. Dis. 2021, 72, 1517–1525. [Google Scholar] [CrossRef] [Scilit]
- Miró, J.M.; Entenza, J.M.; Del Río, A.; Velasco, M.; Castañeda, X.; Garcia de la Mària, C.; Giddey, M.; Armero, Y.; Pericàs, J.M.; Cervera, C.; et al. High-Dose Daptomycin plus Fosfomycin Is Safe and Effective in Treating Methicillin-Susceptible and Methicillin-Resistant Staphylococcus Aureus Endocarditis. Antimicrob. Agents Chemother. 2012, 56, 4511–4515. [Google Scholar] [CrossRef] [Scilit]
- García-de-la-Mària, C.; Gasch, O.; García-Gonzalez, J.; Soy, D.; Shaw, E.; Ambrosioni, J.; Almela, M.; Pericàs, J.M.; Tellez, A.; Falces, C.; et al. The Combination of Daptomycin and Fosfomycin Has Synergistic, Potent, and Rapid Bactericidal Activity against Methicillin-Resistant Staphylococcus Aureus in a Rabbit Model of Experimental Endocarditis. Antimicrob. Agents Chemother. 2018, 62, e02633-17. [Google Scholar] [CrossRef] [Scilit]
- Geriak, M.; Haddad, F.; Rizvi, K.; Rose, W.; Kullar, R.; LaPlante, K.; Yu, M.; Vasina, L.; Ouellette, K.; Zervos, M.; et al. Clinical Data on Daptomycin plus Ceftaroline versus Standard of Care Monotherapy in the Treatment of Methicillin-Resistant Staphylococcus Aureus Bacteremia. Antimicrob. Agents Chemother. 2019, 63, e02483-18. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McCreary, E.K.; Kullar, R.; Geriak, M.; Zasowski, E.J.; Rizvi, K.; Schulz, L.T.; Ouellette, K.; Vasina, L.; Haddad, F.; Rybak, M.J.; et al. Multicenter Cohort of Patients With Methicillin-Resistant Staphylococcus Aureus Bacteremia Receiving Daptomycin Plus Ceftaroline Compared With Other MRSA Treatments. Open Forum Infect. Dis. 2020, 7, ofz538. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nichols, C.N.; Wardlow, L.C.; Coe, K.E.; Sobhanie, M.M.E. Clinical Outcomes With Definitive Treatment of Methicillin-Resistant Staphylococcus Aureus Bacteremia With Retained Daptomycin and Ceftaroline Combination Therapy vs De-Escalation to Monotherapy With Vancomycin, Daptomycin, or Ceftaroline. Open Forum Infect. Dis. 2021, 8, ofab327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Johnson, T.M.; Molina, K.C.; Miller, M.A.; Kiser, T.H.; Huang, M.; Mueller, S.W. Combination Ceftaroline and Daptomycin Salvage Therapy for Complicated Methicillin-Resistant Staphylococcus Aureus Bacteraemia Compared with Standard of Care. Int. J. Antimicrob. Agents 2021, 57, 106310. [Google Scholar] [CrossRef] [Scilit]
- Ahmad, O.; Crawford, T.N.; Myint, T. Comparing the Outcomes of Ceftaroline Plus Vancomycin or Daptomycin Combination Therapy Versus Monotherapy in Adults with Complicated and Prolonged Methicillin-Resistant Staphylococcus Aureus Bacteremia Initially Treated with Supplemental Ceftaroline. Infect. Dis. Ther. 2020, 9, 77–87. [Google Scholar] [CrossRef] [Scilit]
- Sakoulas, G.; Moise, P.A.; Casapao, A.M.; Nonejuie, P.; Olson, J.; Okumura, C.Y.M.; Rybak, M.J.; Kullar, R.; Dhand, A.; Rose, W.E.; et al. Antimicrobial Salvage Therapy for Persistent Staphylococcal Bacteremia Using Daptomycin plus Ceftaroline. Clin. Ther. 2014, 36, 1317–1333. [Google Scholar] [CrossRef] [Scilit]
- Cortes-Penfield, N.; Oliver, N.T.; Hunter, A.; Rodriguez-Barradas, M. Daptomycin and Combination Daptomycin-Ceftaroline as Salvage Therapy for Persistent Methicillin-Resistant Staphylococcus Aureus Bacteremia. Infect. Dis. 2018, 50, 643–647. [Google Scholar] [CrossRef] [Scilit]
- Hornak, J.P.; Anjum, S.; Reynoso, D. Adjunctive Ceftaroline in Combination with Daptomycin or Vancomycin for Complicated Methicillin-Resistant Staphylococcus Aureus Bacteremia after Monotherapy Failure. Ther. Adv. Infect. Dis. 2019, 6, 2049936119886504. [Google Scholar] [CrossRef] [Scilit]
- Duss, F.-R.; Garcia de la Mària, C.; Croxatto, A.; Giulieri, S.; Lamoth, F.; Manuel, O.; Miró, J.M. Successful Treatment with Daptomycin and Ceftaroline of MDR Staphylococcus Aureus Native Valve Endocarditis: A Case Report. J. Antimicrob. Chemother. 2019, 74, 2626–2630. [Google Scholar] [CrossRef] [Scilit]
- Cunha, B.A.; Gran, A. Successful Treatment of Meticillin-Resistant Staphylococcus Aureus (MRSA) Aortic Prosthetic Valve Endocarditis with Prolonged High-Dose Daptomycin plus Ceftaroline Therapy. Int. J. Antimicrob. Agents 2015, 46, 225–226. [Google Scholar] [CrossRef] [Scilit]
- Tascini, C.; Attanasio, V.; Ripa, M.; Carozza, A.; Pallotto, C.; Bernardo, M.; Francisci, D.; Oltolini, C.; Palmiero, G.; Scarpellini, P. Ceftobiprole for the Treatment of Infective Endocarditis: A Case Series. J. Glob. Antimicrob. Resist. 2020, 20, 56–59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oltolini, C.; Castiglioni, B.; Tassan Din, C.; Castiglioni, A.; Ossi, C.; La Canna, G.; Pajoro, U.; Scarpellini, P. Meticillin-Resistant Staphylococcus Aureus Endocarditis: First Report of Daptomycin plus Ceftobiprole Combination as Salvage Therapy. Int. J. Antimicrob. Agents 2016, 47, 502–504. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barber, K.E.; Werth, B.J.; Ireland, C.E.; Stone, N.E.; Nonejuie, P.; Sakoulas, G.; Pogliano, J.; Rybak, M.J. Potent Synergy of Ceftobiprole plus Daptomycin against Multiple Strains of Staphylococcus Aureus with Various Resistance Phenotypes. J. Antimicrob. Chemother. 2014, 69, 3006–3010. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schweizer, M.L.; Richardson, K.; Vaughan Sarrazin, M.S.; Goto, M.; Livorsi, D.J.; Nair, R.; Alexander, B.; Beck, B.F.; Jones, M.P.; Puig-Asensio, M.; et al. Comparative Effectiveness of Switching to Daptomycin Versus Remaining on Vancomycin Among Patients with Methicillin-Resistant Staphylococcus Aureus (MRSA) Bloodstream Infections. Clin. Infect. Dis. 2021, 72, S68–S73. [Google Scholar] [CrossRef] [Scilit]
- Tong, S.Y.C.; Lye, D.C.; Yahav, D.; Sud, A.; Robinson, J.O.; Nelson, J.; Archuleta, S.; Roberts, M.A.; Cass, A.; Paterson, D.L.; et al. Effect of Vancomycin or Daptomycin With vs Without an Antistaphylococcal β-Lactam on Mortality, Bacteremia, Relapse, or Treatment Failure in Patients With MRSA Bacteremia: A Randomized Clinical Trial. JAMA 2020, 323, 527–537. [Google Scholar] [CrossRef] [Scilit]
- Ryder, J.H.; Tong, S.Y.C.; Gallagher, J.C.; McDonald, E.G.; Thevarajan, I.; Lee, T.C.; Cortés-Penfield, N.W. Deconstructing the Dogma: Systematic Literature Review and Meta-Analysis of Adjunctive Gentamicin and Rifampin in Staphylococcal Prosthetic Valve Endocarditis. Open Forum Infect. Dis. 2022, 9, ofac583. [Google Scholar] [CrossRef] [Scilit]
- Sotgiu, G.; Aliberti, S.; Gramegna, A.; Mantero, M.; Di Pasquale, M.; Trogu, F.; Saderi, L.; Blasi, F. Efficacy and Effectiveness of Ceftaroline Fosamil in Patients with Pneumonia: A Systematic Review and Meta-Analysis. Respir. Res. 2018, 19, 205. [Google Scholar] [CrossRef] [Scilit]
- Bassetti, M.; Russo, A.; Cilloniz, C.; Giacobbe, D.R.; Vena, A.; Amaro, R.; Graziano, E.; Soriano, A.; Torres, A. Ceftaroline for Severe Community-Acquired Pneumonia: A Real-World Two-Centre Experience in Italy and Spain. Int. J. Antimicrob. Agents 2020, 55, 105921. [Google Scholar] [CrossRef] [Scilit]
- Nicholson, S.C.; Welte, T.; File, T.M.; Strauss, R.S.; Michiels, B.; Kaul, P.; Balis, D.; Arbit, D.; Amsler, K.; Noel, G.J. A Randomised, Double-Blind Trial Comparing Ceftobiprole Medocaril with Ceftriaxone with or without Linezolid for the Treatment of Patients with Community-Acquired Pneumonia Requiring Hospitalisation. Int. J. Antimicrob. Agents 2012, 39, 240–246. [Google Scholar] [CrossRef] [Scilit]
- Durante-Mangoni, E.; Andini, R.; Mazza, M.C.; Sangiovanni, F.; Bertolino, L.; Ursi, M.P.; Paradiso, L.; Karruli, A.; Esposito, C.; Murino, P.; et al. Real-Life Experience with Ceftobiprole in a Tertiary-Care Hospital. J. Glob. Antimicrob. Resist. 2020, 22, 386–390. [Google Scholar] [CrossRef] [Scilit]
- Riccobene, T.A.; Pushkin, R.; Jandourek, A.; Knebel, W.; Khariton, T. Penetration of Ceftaroline into the Epithelial Lining Fluid of Healthy Adult Subjects. Antimicrob. Agents Chemother. 2016, 60, 5849–5857. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rodvold, K.A.; Nicolau, D.P.; Lodise, T.P.; Khashab, M.; Noel, G.J.; Kahn, J.B.; Gotfried, M.; Murray, S.A.; Nicholson, S.; Laohavaleeson, S.; et al. Identifying Exposure Targets for Treatment of Staphylococcal Pneumonia with Ceftobiprole. Antimicrob. Agents Chemother. 2009, 53, 3294–3301. [Google Scholar] [CrossRef] [Scilit]
- Edlinger-Stanger, M.; Al Jalali, V.; Andreas, M.; Jäger, W.; Böhmdorfer, M.; Zeitlinger, M.; Hutschala, D. Plasma and Lung Tissue Pharmacokinetics of Ceftaroline Fosamil in Patients Undergoing Cardiac Surgery with Cardiopulmonary Bypass: An In Vivo Microdialysis Study. Antimicrob. Agents Chemother. 2021, 65, e0067921. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chauzy, A.; Gregoire, N.; Ferrandière, M.; Lasocki, S.; Ashenoune, K.; Seguin, P.; Boisson, M.; Couet, W.; Marchand, S.; Mimoz, O.; et al. Population Pharmacokinetic/Pharmacodynamic Study Suggests Continuous Infusion of Ceftaroline Daily Dose in Ventilated Critical Care Patients with Early-Onset Pneumonia and Augmented Renal Clearance. J. Antimicrob. Chemother. 2022, 77, 3173–3179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vazquez, J.A.; Maggiore, C.R.; Cole, P.; Smith, A.; Jandourek, A.; Friedland, H.D. Ceftaroline Fosamil for the Treatment of Staphylococcus Aureus Bacteremia Secondary to Acute Bacterial Skin and Skin Structure Infections or Community-Acquired Bacterial Pneumonia. Infect. Dis. Clin. Pr. 2015, 23, 39–43. [Google Scholar] [CrossRef] [Scilit]
- Kato, H.; Hagihara, M.; Asai, N.; Shibata, Y.; Koizumi, Y.; Yamagishi, Y.; Mikamo, H. Meta-Analysis of Vancomycin versus Linezolid in Pneumonia with Proven Methicillin-Resistant Staphylococcus Aureus. J. Glob. Antimicrob. Resist. 2021, 24, 98–105. [Google Scholar] [CrossRef] [Scilit]
- Jiang, H.; Tang, R.-N.; Wang, J. Linezolid versus Vancomycin or Teicoplanin for Nosocomial Pneumonia: Meta-Analysis of Randomised Controlled Trials. Eur. J. Clin. Microbiol. Infect. Dis. 2013, 32, 1121–1128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Antonello, R.M.; Principe, L.; Maraolo, A.E.; Viaggi, V.; Pol, R.; Fabbiani, M.; Montagnani, F.; Lovecchio, A.; Luzzati, R.; Di Bella, S. Fosfomycin as Partner Drug for Systemic Infection Management. A Systematic Review of Its Synergistic Properties from In Vitro and In Vivo Studies. Antibiotics 2020, 9, E500. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, L.; Chen, H.; Liu, Y.; Xu, S.; Wu, M.; Liu, Z.; Qi, C.; Zhang, G.; Li, J.; Huang, X. Synergistic Effect of Linezolid with Fosfomycin against Staphylococcus Aureus in Vitro and in an Experimental Galleria Mellonella Model. J. Microbiol. Immunol. Infect. 2020, 53, 731–738. [Google Scholar] [CrossRef] [Scilit]
- Chen, H.; Li, L.; Liu, Y.; Wu, M.; Xu, S.; Zhang, G.; Qi, C.; Du, Y.; Wang, M.; Li, J.; et al. In Vitro Activity and Post-Antibiotic Effects of Linezolid in Combination with Fosfomycin against Clinical Isolates of Staphylococcus Aureus. Infect. Drug Resist. 2018, 11, 2107–2115. [Google Scholar] [CrossRef] [Scilit]
- Chai, D.; Liu, X.; Wang, R.; Bai, Y.; Cai, Y. Efficacy of Linezolid and Fosfomycin in Catheter-Related Biofilm Infection Caused by Methicillin-Resistant Staphylococcus Aureus. Biomed Res. Int. 2016, 2016, 6413982. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xie, N.; Jiang, L.; Chen, M.; Zhang, G.; Liu, Y.; Li, J.; Huang, X. In Vitro and in Vivo Antibacterial Activity of Linezolid Plus Fosfomycin Against Staphylococcus Aureus with Resistance to One Drug. Infect. Drug Resist. 2021, 14, 639–649. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kaye, K.S.; Udeani, G.; Cole, P.; Friedland, H.D. Ceftaroline Fosamil for the Treatment of Hospital-Acquired Pneumonia and Ventilator-Associated Pneumonia. Hosp. Pr. 2015, 43, 144–149. [Google Scholar] [CrossRef] [Scilit]
- Scheeren, T.W.L.; Welte, T.; Saulay, M.; Engelhardt, M.; Santerre-Henriksen, A.; Hamed, K. Early Improvement in Severely Ill Patients with Pneumonia Treated with Ceftobiprole: A Retrospective Analysis of Two Major Trials. BMC Infect. Dis. 2019, 19, 195. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Antonelli, A.; Giani, T.; Coppi, M.; Di Pilato, V.; Arena, F.; Colavecchio, O.L.; Conte, V.; Santerre Henriksen, A.; Rossolini, G.M.; MRSA-HAP Study Group; et al. Staphylococcus Aureus from Hospital-Acquired Pneumonia from an Italian Nationwide Survey: Activity of Ceftobiprole and Other Anti-Staphylococcal Agents, and Molecular Epidemiology of Methicillin-Resistant Isolates. J. Antimicrob. Chemother. 2019, 74, 3453–3461. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Conte, J.E.; Golden, J.A.; Kipps, J.; Zurlinden, E. Intrapulmonary Pharmacokinetics of Linezolid. Antimicrob. Agents Chemother. 2002, 46, 1475–1480. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, C.; Zhang, X.; Xie, J.; Li, Q.; He, J.; Hu, L.; Wang, H.; Liu, A.; Xu, J.; Yang, C.; et al. Pharmacokinetic/Pharmacodynamic Parameters of Linezolid in the Epithelial Lining Fluid of Patients With Sepsis. J. Clin. Pharmacol. 2022, 62, 891–897. [Google Scholar] [CrossRef] [Scilit]
- Boselli, E.; Breilh, D.; Caillault-Sergent, A.; Djabarouti, S.; Guillaume, C.; Xuereb, F.; Bouvet, L.; Rimmelé, T.; Saux, M.-C.; Allaouchiche, B. Alveolar Diffusion and Pharmacokinetics of Linezolid Administered in Continuous Infusion to Critically Ill Patients with Ventilator-Associated Pneumonia. J. Antimicrob. Chemother. 2012, 67, 1207–1210. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matzi, V.; Lindenmann, J.; Porubsky, C.; Kugler, S.A.; Maier, A.; Dittrich, P.; Smolle-Jüttner, F.M.; Joukhadar, C. Extracellular Concentrations of Fosfomycin in Lung Tissue of Septic Patients. J. Antimicrob. Chemother. 2010, 65, 995–998. [Google Scholar] [CrossRef] [Scilit]
- Chen, H.-A.; Yang, C.-J.; Tsai, M.-S.; Liao, C.-H.; Lee, C.-H. Linezolid as Salvage Therapy for Central Nervous System Infections Due to Methicillin-Resistant Staphylococcus Aureus at Two Medical Centers in Taiwan. J. Microbiol. Immunol. Infect. 2020, 53, 909–915. [Google Scholar] [CrossRef] [Scilit]
- Pintado, V.; Pazos, R.; Jiménez-Mejías, M.E.; Rodríguez-Guardado, A.; Díaz-Pollán, B.; Cabellos, C.; García-Lechuz, J.M.; Lora-Tamayo, J.; Domingo, P.; Muñez, E.; et al. Linezolid for Therapy of Staphylococcus Aureus Meningitis: A Cohort Study of 26 Patients. Infect. Dis. 2020, 52, 808–815. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sipahi, O.R.; Bardak-Ozcem, S.; Turhan, T.; Arda, B.; Ruksen, M.; Pullukcu, H.; Aydemir, S.; Dalbasti, T.; Yurtseven, T.; Sipahi, H.; et al. Vancomycin versus Linezolid in the Treatment of Methicillin-Resistant Staphylococcus Aureus Meningitis. Surg. Infect. 2013, 14, 357–362. [Google Scholar] [CrossRef] [Scilit]
- Rebai, L.; Fitouhi, N.; Daghmouri, M.A.; Bahri, K. Linezolid for the Treatment of Postneurosurgical Infection Caused by Methicillin-Resistant Staphylococcus. Surg. Neurol. Int. 2019, 10, 215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saito, N.; Aoki, K.; Sakurai, T.; Ito, K.; Hayashi, M.; Hirata, Y.; Sato, K.; Harashina, J.; Akahata, M.; Iwabuchi, S. Linezolid Treatment for Intracranial Abscesses Caused by Methicillin-Resistant Staphylococcus Aureus--Two Case Reports. Neurol. Med. Chir. 2010, 50, 515–517. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kallweit, U.; Harzheim, M.; Marklein, G.; Welt, T.; Pöhlau, D. Successful Treatment of Methicillin-Resistant Staphylococcus Aureus Meningitis Using Linezolid without Removal of Intrathecal Infusion Pump. Case Report. J. Neurosurg. 2007, 107, 651–653. [Google Scholar] [CrossRef] [Scilit]
- Kessler, A.T.; Kourtis, A.P. Treatment of Meningitis Caused by Methicillin-Resistant Staphylococcus Aureus with Linezolid. Infection 2007, 35, 271–274. [Google Scholar] [CrossRef] [Scilit]
- Viale, P.; Pagani, L.; Cristini, F.; Stefini, R.; Bergomi, R.; Colombini, P.; Carosi, G. Linezolid for the Treatment of Central Nervous System Infections in Neurosurgical Patients. Scand. J. Infect. Dis. 2002, 34, 456–459. [Google Scholar] [CrossRef] [Scilit]
- Viaggi, B.; Paolo, A.D.; Danesi, R.; Polillo, M.; Ciofi, L.; Del Tacca, M.; Malacarne, P. Linezolid in the Central Nervous System: Comparison between Cerebrospinal Fluid and Plasma Pharmacokinetics. Scand. J. Infect. Dis. 2011, 43, 721–727. [Google Scholar] [CrossRef] [Scilit]
- Pfausler, B.; Spiss, H.; Dittrich, P.; Zeitlinger, M.; Schmutzhard, E.; Joukhadar, C. Concentrations of Fosfomycin in the Cerebrospinal Fluid of Neurointensive Care Patients with Ventriculostomy-Associated Ventriculitis. J. Antimicrob. Chemother. 2004, 53, 848–852. [Google Scholar] [CrossRef] [Scilit]
- Samura, M.; Kitahiro, Y.; Tashiro, S.; Moriyama, H.; Hamamura, Y.; Takahata, I.; Kawabe, R.; Enoki, Y.; Taguchi, K.; Takesue, Y.; et al. Efficacy and Safety of Daptomycin versus Vancomycin for Bacteremia Caused by Methicillin-Resistant Staphylococcus aureus with Vancomycin Minimum Inhibitory Concentration > 1 µg/mL: A Systematic Review and Meta-Analysis. Pharmaceutics 2022, 14, 714. [Google Scholar] [CrossRef] [Scilit]
- Cogo, A.; Gonzalez-Ruiz, A.; Pathan, R.; Hamed, K. Real-World Treatment of Complicated Skin and Soft Tissue Infections with Daptomycin: Results from a Large European Registry (EU-CORE). Infect. Dis. Ther. 2015, 4, 273–282. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heath, D.M.; Boyer, B.J.; Ghali, A.N.; Momtaz, D.A.; Nagel, S.C.; Brady, C.I. Use of Clindamycin for Necrotizing Soft Tissue Infection Decreases Amputation Rate. J. Orthop. Trauma 2022, 36, 327–331. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gatti, M.; Gasparini, L.E.; Laratta, M.; Sigurtà, A.; Rossi, A.; Brioschi, P.; Chiara, O.; Vismara, C.; Scaglione, F.; Arlati, S. Intensive Multidisciplinary Management in Critical Care Patients Affected by Severe Necrotizing Soft Tissue Infections: A Cooperative Method to Improve the Efficacy of Treatment. Eur. J. Clin. Microbiol. Infect. Dis. 2019, 38, 1153–1162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kim, A.; Suecof, L.A.; Sutherland, C.A.; Gao, L.; Kuti, J.L.; Nicolau, D.P. In Vivo Microdialysis Study of the Penetration of Daptomycin into Soft Tissues in Diabetic versus Healthy Volunteers. Antimicrob. Agents Chemother. 2008, 52, 3941–3946. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Traunmüller, F.; Schintler, M.V.; Metzler, J.; Spendel, S.; Mauric, O.; Popovic, M.; Konz, K.H.; Scharnagl, E.; Joukhadar, C. Soft Tissue and Bone Penetration Abilities of Daptomycin in Diabetic Patients with Bacterial Foot Infections. J. Antimicrob. Chemother. 2010, 65, 1252–1257. [Google Scholar] [CrossRef] [Scilit]
- Ramanan, P.; Bryson, A.L.; Binnicker, M.J.; Pritt, B.S.; Patel, R. Syndromic Panel-Based Testing in Clinical Microbiology. Clin. Microbiol. Rev. 2018, 31, e00024-17. [Google Scholar] [CrossRef] [Scilit]
- Gatti, M.; Pea, F. Pharmacokinetic/Pharmacodynamic Target Attainment in Critically Ill Renal Patients on Antimicrobial Usage: Focus on Novel Beta-Lactams and Beta Lactams/Beta-Lactamase Inhibitors. Expert Rev. Clin. Pharmacol. 2021, 14, 583–599. [Google Scholar] [CrossRef] [Scilit]
- Galar, A.; Weil, A.A.; Dudzinski, D.M.; Muñoz, P.; Siedner, M.J. Methicillin-Resistant Staphylococcus Aureus Prosthetic Valve Endocarditis: Pathophysiology, Epidemiology, Clinical Presentation, Diagnosis, and Management. Clin. Microbiol. Rev. 2019, 32, e00041-18. [Google Scholar] [CrossRef] [Scilit]
- Mishra, N.N.; Lew, C.; Abdelhady, W.; Lapitan, C.K.; Proctor, R.A.; Rose, W.E.; Bayer, A.S. Synergy Mechanisms of Daptomycin-Fosfomycin Combinations in Daptomycin-Susceptible and -Resistant Methicillin-Resistant Staphylococcus Aureus: In Vitro, Ex Vivo, and In Vivo Metrics. Antimicrob. Agents Chemother. 2022, 66, e0164921. [Google Scholar] [CrossRef] [Scilit]
- Eliazar, J.; Johnson, T.; Chbib, C. Pre-Clinical Impact of the Synergistic Mechanism of Daptomycin and Ceftaroline on Patients with Methicillin-Resistant Staphylococcus Aureus Bacteremia Infections. Curr. Rev. Clin. Exp. Pharmacol. 2021, 16, 296–299. [Google Scholar] [CrossRef] [Scilit]
- Fu, Z.; Ma, Y.; Chen, C.; Guo, Y.; Hu, F.; Liu, Y.; Xu, X.; Wang, M. Prevalence of Fosfomycin Resistance and Mutations in MurA, GlpT, and UhpT in Methicillin-Resistant Staphylococcus Aureus Strains Isolated from Blood and Cerebrospinal Fluid Samples. Front. Microbiol. 2015, 6, 1544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, Y.-C.; Chen, P.-Y.; Wang, J.-T.; Chang, S.-C. Prevalence of Fosfomycin Resistance and Gene Mutations in Clinical Isolates of Methicillin-Resistant Staphylococcus Aureus. Antimicrob. Resist. Infect. Control. 2020, 9, 135. [Google Scholar] [CrossRef] [Scilit]
- Harrison, E.M.; Ba, X.; Blane, B.; Ellington, M.J.; Loeffler, A.; Hill, R.L.R.; Holmes, M.A.; Peacock, S.J. PBP2a Substitutions Linked to Ceftaroline Resistance in MRSA Isolates from the UK. J. Antimicrob. Chemother. 2016, 71, 268–269. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, H.; Yoon, E.-J.; Kim, D.; Kim, J.W.; Lee, K.-J.; Kim, H.S.; Kim, Y.R.; Shin, J.H.; Shin, J.H.; Shin, K.S.; et al. Ceftaroline Resistance by Clone-Specific Polymorphism in Penicillin-Binding Protein 2a of Methicillin-Resistant Staphylococcus Aureus. Antimicrob. Agents Chemother. 2018, 62, e00485-18. [Google Scholar] [CrossRef] [Scilit]
- Jacob, J.T.; DiazGranados, C.A. High Vancomycin Minimum Inhibitory Concentration and Clinical Outcomes in Adults with Methicillin-Resistant Staphylococcus Aureus Infections: A Meta-Analysis. Int. J. Infect. Dis. 2013, 17, e93–e100. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miyazaki, M.; Takata, T.; Yoshimura, H.; Matsunaga, A.; Ohta, D.; Ishikura, H.; Futo, M.; Hara, S.; Kamimura, H.; Tamura, K.; et al. Vancomycin Bactericidal Activity as a Predictor of 30-Day Mortality in Patients with Methicillin-Resistant Staphylococcus Aureus Bacteremia. Antimicrob. Agents Chemother. 2011, 55, 1819–1820. [Google Scholar] [CrossRef] [Scilit]
- Kan, W.-C.; Chen, Y.-C.; Wu, V.-C.; Shiao, C.-C. Vancomycin-Associated Acute Kidney Injury: A Narrative Review from Pathophysiology to Clinical Application. Int. J. Mol. Sci. 2022, 23, 2052. [Google Scholar] [CrossRef] [Scilit]
- Luque, S.; Grau, S.; Alvarez-Lerma, F.; Ferrández, O.; Campillo, N.; Horcajada, J.P.; Basas, M.; Lipman, J.; Roberts, J.A. Plasma and Cerebrospinal Fluid Concentrations of Linezolid in Neurosurgical Critically Ill Patients with Proven or Suspected Central Nervous System Infections. Int. J. Antimicrob. Agents 2014, 44, 409–415. [Google Scholar] [CrossRef] [Scilit]
- Sartelli, M.; Guirao, X.; Hardcastle, T.C.; Kluger, Y.; Boermeester, M.A.; Raşa, K.; Ansaloni, L.; Coccolini, F.; Montravers, P.; Abu-Zidan, F.M.; et al. 2018 WSES/SIS-E Consensus Conference: Recommendations for the Management of Skin and Soft-Tissue Infections. World J. Emerg. Surg. 2018, 13, 58. [Google Scholar] [CrossRef] [Scilit]
- Gatti, M.; Pea, F. Should the Clinical Pharmacologist Play a Role in the Multidisciplinary Team Managing Severe Necrotizing Soft-Tissue Infections? Clin. Pharmacokinet. 2021, 60, 403–407. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).