


Abstract
Background/Objectives: Functional dyspepsia (FD) is a gastrointestinal disorder typically treated by changes in diet and lifestyle. However, in the Colombian population, few studies have addressed its etiology and diagnosis. This exploratory study aimed to identify predictive variables associated with the presence of dyspeptic symptoms (DS). Methods: To address this, a self-survey was conducted evaluating sociodemographic characteristics, clinical history, and dietary habits. A DS index was calculated using participant’s clinical history to explore the characteristics of the groups with more and less DS (MDS and LDS groups). Additionally, a regression model was applied to identify the predictors of higher DS scores. Pooled data from the rolling, cross-sectional eating habits and DS survey between May and July of 2024. We enrolled 102 Colombian participants between 18 and 65 years old. Results: Significant differences were identified between MDS and LDS groups in occupation and dietary habits, with students exhibiting a higher DS index. Moreover, MDS exhibited greater consumption of fatty and fried foods than LDS groups. Regression analysis revealed that high intake of fatty foods and sesame were the best predictors of higher DS index. In contrast, the consumption of Saccharomyces boulardii probiotic and white onion was associated with better gastrointestinal health. Conclusions: Changes in dietary habits are associated with lower DS; the effect and its etiology might also depend on the participants’ occupation and nutritional habits.
1. Introduction
Functional dyspepsia (FD) is one of the most common multifactorial gastrointestinal disorders, affecting 8.4% of the global population, with a higher prevalence in women than in men [1,2,3,4,5]. FD is often underdiagnosed and undertreated [6]. The chronic or recurrent gastrointestinal symptoms of FD include pain, burning, bloating, early satiety, fullness, belching, nausea, or vomiting, without structural disease to explain them. These symptoms must occur at least three times per week for three to six months before diagnosis [3,4,7,8,9,10].
FD is currently divided into two subgroups based on the primary clinical pattern: postprandial distress syndrome (PDS) and epigastric pain syndrome (EPS). Some authors propose a third subgroup consisting of overlapping symptoms, referred to as PDS-EPS [3,4,7,8,9,11]. Consumption of certain foods typically triggers PDS and presents symptoms such as postprandial fullness, early satiety, loss of appetite, nausea, vomiting, and abdominal bloating. In contrast, EPS is characterized by epigastric pain or burning that occurs independently of food intake [2,7].
An FD diagnosis is established through a comprehensive medical history and physical examination during the critical period when the symptoms are present. Experts rely on the updated Rome IV criteria for functional gastrointestinal disorders to guide the diagnostic process, often supplemented with in situ tests. The gold standard for diagnosis is upper endoscopy with biopsy, which enables determination of the disease’s origin and severity [4,7,9]. Patients with FD commonly exhibit eosinophilic infiltration in the duodenum, particularly in cases of postprandial distress syndrome (PDS). Additionally, FD has been associated with circulating T cells in the small intestine, elevated cytokine levels, and elevated tumor necrosis factor-α (TNF-α) levels, suggesting underlying intestinal inflammation [12]. Other key contributors to FD pathophysiology include abnormal central modulation, visceral hypersensitivity, and increased intestinal mucosal permeability, often linked to disruptions in the gut brain axis [7].
FD treatment typically involves dietary and lifestyle modifications, pharmacological therapy such as proton pump inhibitors (PPIs), and, in some cases, psychological treatment depending on the underlying cause [2,7,8]. Treatment remains challenging due to the unclear etiology of dyspepsia. However, certain factors have been associated with the condition, including chronic use of nonsteroidal anti-inflammatory drugs (NSAIDs), consumption of highly spiced foods, Helicobacter pylori infection acquired through contaminated food, lack of access to clean drinking water, and other environmental factors [4,7,8,10,11,13,14].
Previous studies have demonstrated a significant impact of dietary habits on FD pathophysiology, triggering or exacerbating symptoms such as postprandial fullness, early satiety, epigastric pain, acid and duodenal hypersensitivity, food allergies, and intolerance or sensitivity to certain foods [5,7,11]. These symptoms have been associated with increased caloric intake and inadequate eating behaviors, such as late-night consumption of processed snacks, consistently skipping one or more meals, frequent intake of large portions, high liquid intake while fasting, and rapid eating without proper chewing [5,15]. An imbalance in macronutrient consumption, such as high-fat, protein, or simple carbohydrate diets, has been associated with the exacerbation of dyspeptic symptoms (DS). Moreover, specific foods have been involved in DS, including spicy foods, industrialized juices, carbonated beverages, wheat products, gluten, legumes, watermelon, red peppers, caffeinated products, tea, alcohol, chocolate, processed meats, vinegar-based pickles, salty food, macaroni, fast food, and acidic foods [7,11,15,16]. On the other hand, certain foods and supplements have been recognized to alleviate DS, including acid suppressants, prokinetics, and neuromodulators, as well as fruits such as apples, rice, yogurt, honey, rock sugar, bread, caraway seeds, quince, and nuts [16]. Other effective options include ginger [17], medicinal herbs [18,19], nutraceutical supplements containing perilla and ginger extracts [20], supplements with ginger and artichoke extracts [21], and mastic gum, among others [7,11,16,22].
Recent studies indicate that a significant proportion of the Colombian population experiences DS, particularly in urban areas. According to the Ipsos Global Health Services Monitor, 84% of Colombians reported digestive discomfort related to imbalances in the gut microbiota, which contribute to DS. The prevalence of this condition varies across cities in the country, with Barranquilla and Medellín reporting the highest rates, followed by Bogotá and Cali. Despite its high prevalence, FD in Colombia remains underdiagnosed. Many patients do not seek medical attention due to the normalization of digestive symptoms or limited access to specialized healthcare.
Furthermore, appropriate treatment is not always available, and empirical treatments often target symptoms without considering the underlying cause of DS. The gap in healthcare access between urban and rural areas exacerbates the situation. People living in rural or underserved regions face significant barriers to obtaining proper diagnosis and treatment, worsening the dyspepsia situation.
Therefore, this study had two primary aims: the first was to characterize differences between participants with more and less DS in sociodemographic, environmental, and dietary factors, and gastrointestinal and non-communicable diseases (such as diabetes and hypertension). The second, equally important, was to explore predictor variables related to eating habits that increase the risk of DS in the Colombian population.
2. Materials and Methods
2.1. Participants
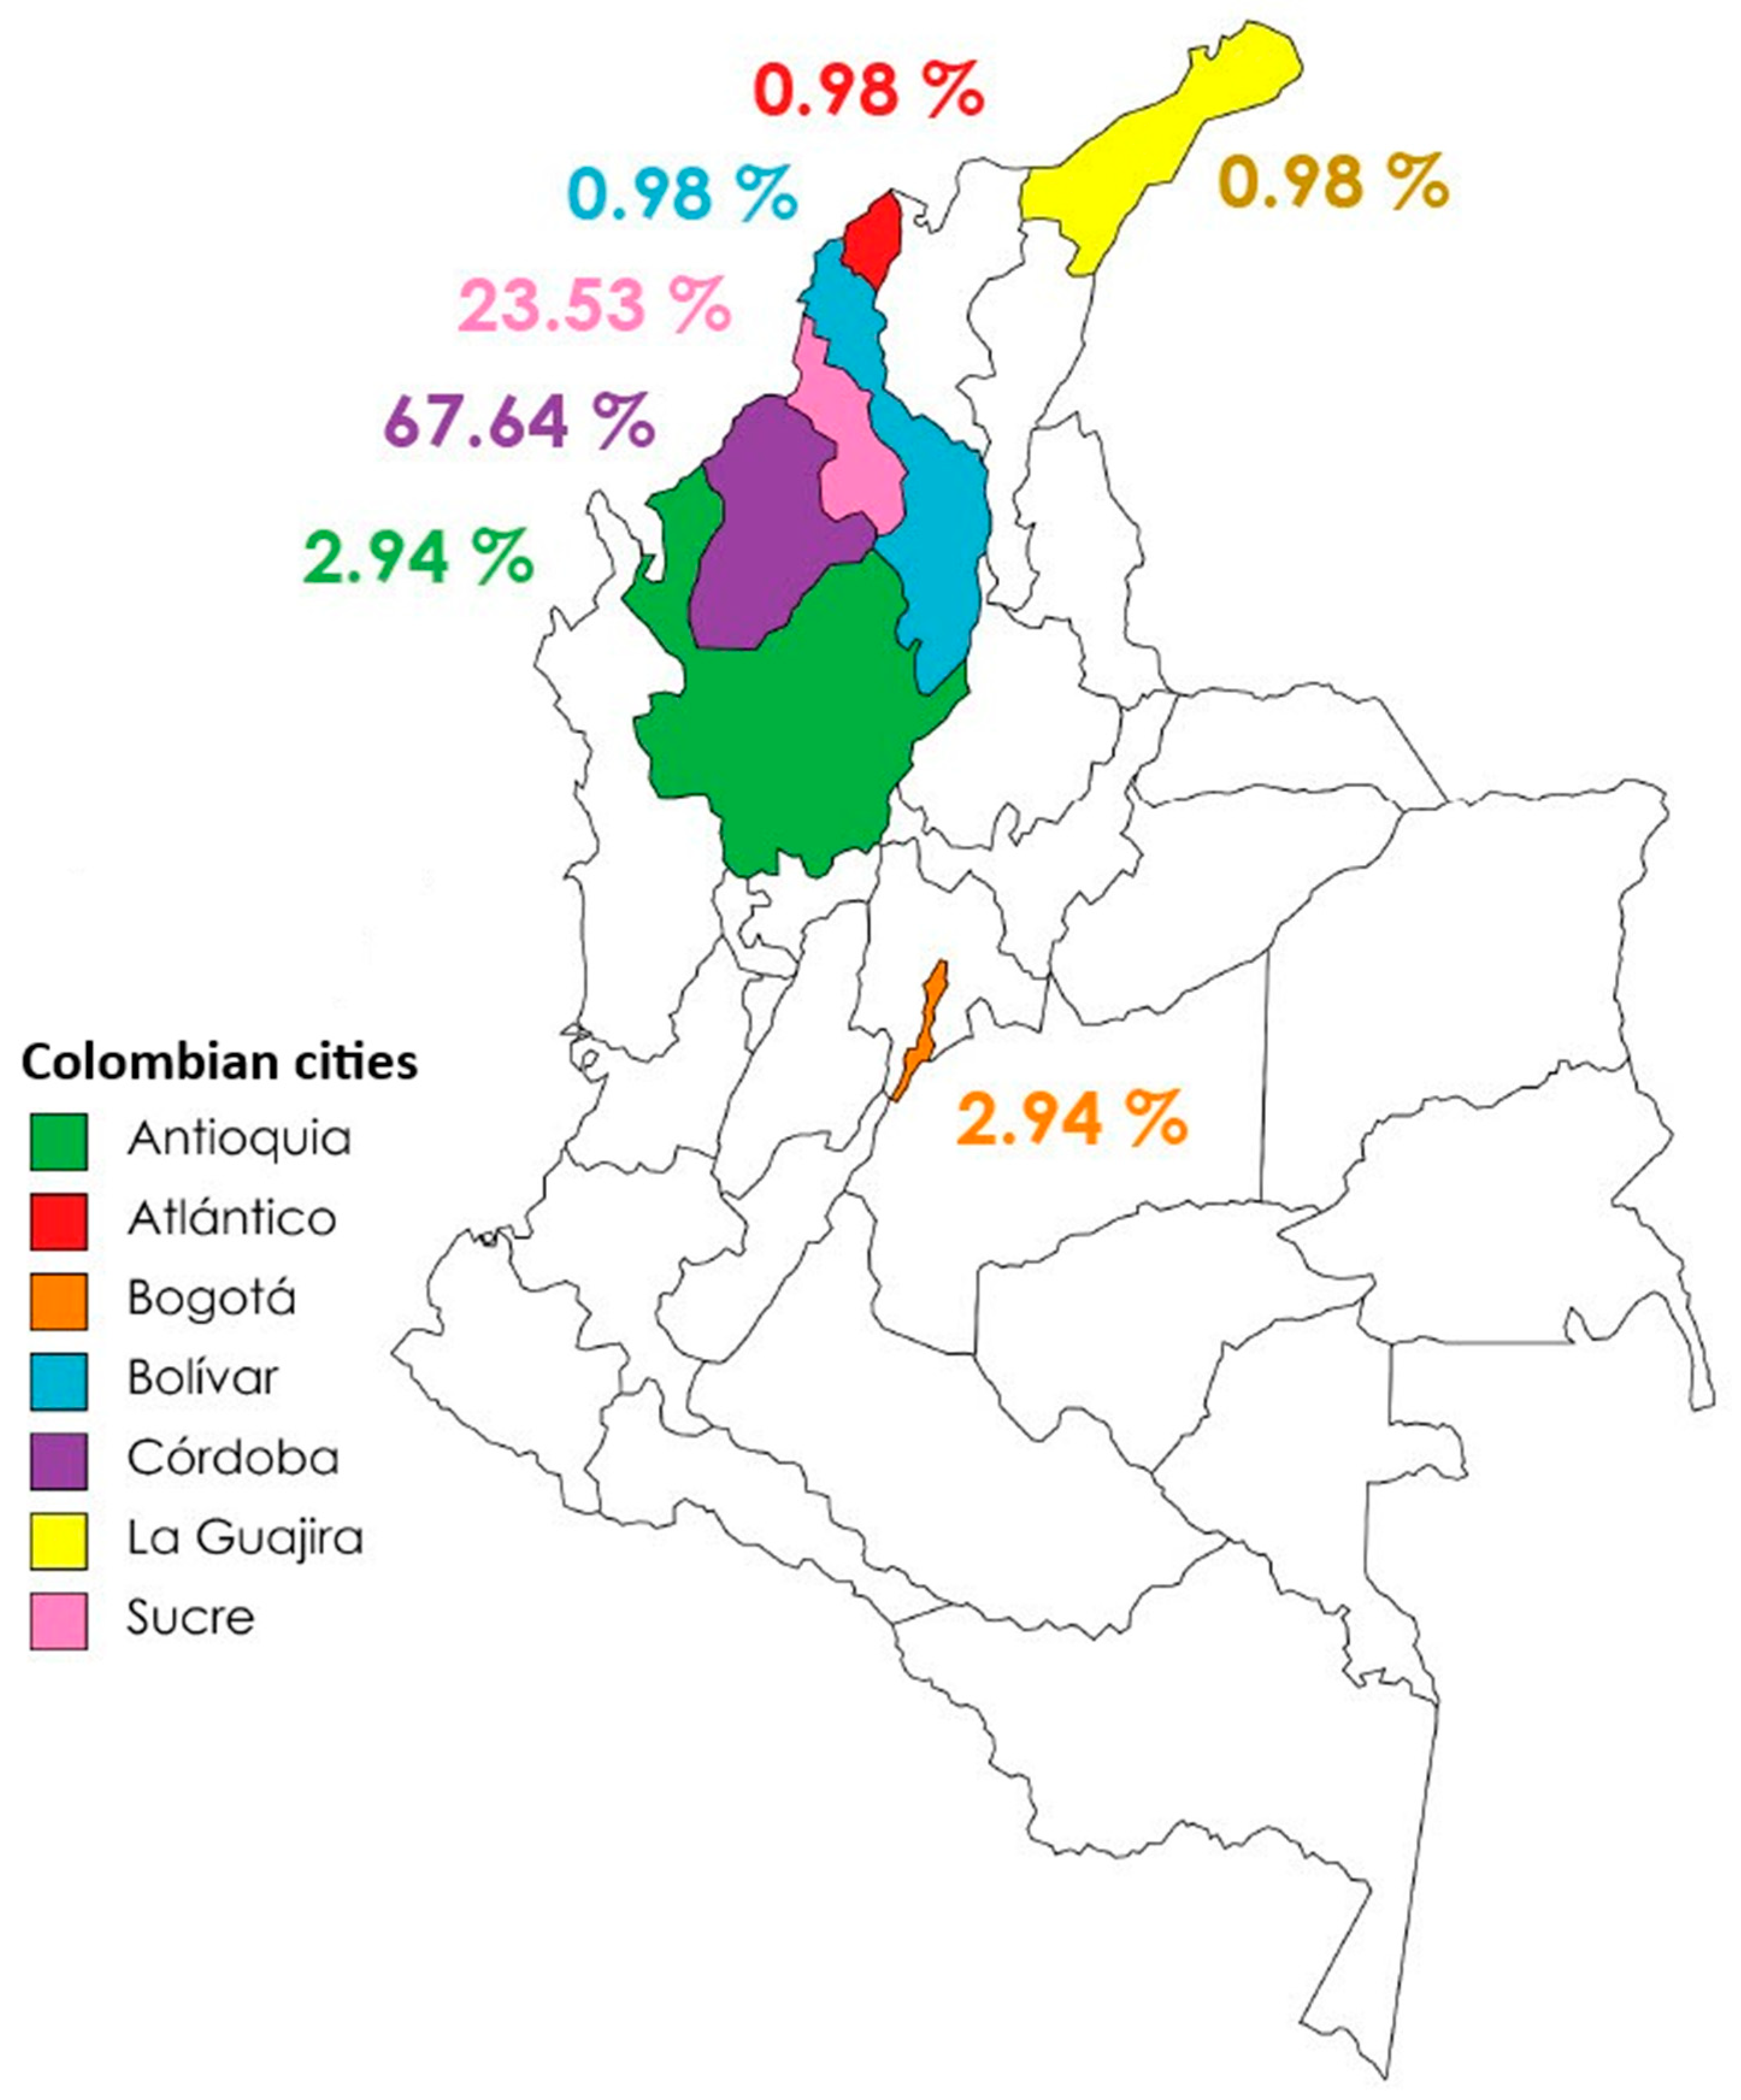
The present study enrolled 102 Colombian participants aged 18 to 65 years. All of them are native Spanish speakers with at least 9 years of scholarship and internet access. In this study, health condition was assessed through an online survey; therefore, volunteers were not examined by a physician. The participants who stated they suffered from chronic diseases such as cancer or Helicobacter pylori infection were excluded from this study. The sample was randomly selected in different regions in Colombia (see Appendix A). The study was conducted in accordance with the Declaration of Helsinki, and participants were informed of their rights and provided written informed consent to participate. The results are part of the protocol approved by the BUAP, registration number 042.
2.2. Procedure
The data were obtained from a self-administered survey directed to the Colombian population. This entailed 55 items distributed in four sections: (1) identification data; (2) anthropometric data; (3) medical records; and (4) food intake frequency in the last month, including fruits, vegetables, cereals, legumes, spices, and beverages (See Appendix B). The present study employed an exploratory, cross-sectional design and used non-probabilistic convenience sampling. A pilot group of 40 subjects participated in the survey; all participants reported a thorough understanding of the items. They also reported being comfortable with the process and the completion time. The pilot group responded to 100% of the questions in around 25 min. We performed a statistical analysis to validate the survey using a chi-square test. The factor analysis technique used an orthogonal rotation, “Varimax”. We also measured the internal consistency of each item within each factor using Cronbach’s alpha (0.857). We also computed the Kaiser–Meyer–Olkin (KMO) statistics (0.748) and Bartlett’s sphericity test (X2 (21) 468.295, p = 0.0001). A DS index was generated to assess symptom severity based on participants’ responses to our survey (see Table 1).
Table 1.
DS index calculation.
Additionally, the DS index positively correlated with the ROMA IV criteria (Bristol scale, bowel moving frequency) (p = 0.04), which might support preliminary convergent validity of our DS index.
2.3. Data Analysis Methods
2.3.1. Cluster Analysis
To explore this study’s first aim. A K-means clustering was performed to separate our sample into two groups. The clustering analyses resulted in 69 participants (Mean (M) = 30.0, ±2.7; range: 23–38) with a higher DS score (MDS) and 33 participants (M = 13.3, ±3.8; range: 4–21) with a lower DS score (LDS). After bootstrap analysis conducted with a sample size of 1000, significant differences in DS scores remain between the MDS and LDS groups (t(100,47) = 24.3, p = 0.000).
2.3.2. Comparisons Between Less vs. More DS (LDS vs. MDS)
Some conditions, such as sex, civil status, scholarship, occupation, and frequency of food consumption, were compared between DS groups using aχ2 test (i.e., vegetables, fruits, red meat, white meat, eggs, dairy products, soft drinks, pasta, and fast food). We also compared the frequency of consumption of fatty foods (i.e., arepas, fried foods, fritanga, buñuelos, cakes) between groups using aχ2 test. The age was compared between groups with the Mann–Whitney U test (Kolmogorov–Smirnov test, p = 0.001), and body mass index (BMI) with the t-test (Kolmogorov–Smirnov test, p = 0.2). The Kendall Tau-C model was also calculated to explore the relationship between DS groups (i.e., LDS and MDS) and BMI category. p-values resulting from a set of comparisons were corrected by the FDR method. We report results surviving FDR correction (p-values < 0.05).
2.3.3. Exploratory Predictors of the DS Index
Linear regression analysis was performed to identify the relationship between the DS index and demographic, anthropometric data (BMI), comorbidities, and the frequency of food consumption. The DS index was included as the dependent variable. Sex, age, and scholarship, diseases (i.e., diabetes, hypertension, hypercholesterolemia, hypertriglyceridemia, nonspecific ulcerative colitis (UC), irritable bowel syndrome, and obesity, drug addiction), frequency of consumption of food (i.e., fruits, vegetables, red and white meats, spices, cereals, legumes, fermented foods and commercial products containing probiotics) were included as independent variables. The Kolmogorov–Smirnov test was used to assess the normality of the variables. Descriptive analyses were performed, and the results are presented as means and standard deviations (SD), as well as proportions and/or percentages, depending on the type of variable analyzed. The (χ2) test was used to compare categorical variables, e.g., BMI vs. DS Index (dichotomous). A regression analysis was conducted to identify which variables positively or negatively predict the outcome variable of interest (DS). We performed a multicollinearity analysis before including predictor variables in the regression model, following the next tests: correlation analyses, tolerance values, variance inflation factors, and condition indices. Variables with values outside the parameter range were excluded from the regression analysis (see Supplementary Materials).
3. Results
3.1. Participant Characteristics
Table 2 illustrates demographic, anthropometric, and distribution of non-communicable diseases for LDS and MDS groups.
Table 2.
Demographic, anthropometric, and non-communicable disease data for the LDS and MDS groups.
3.2. Demographic and Anthropometric Comparisons Between LDS and MDS Groups
Analyzing our results, shown that the DS groups did not differ in sex (χ2 (1) 0.4, p = 0.5), civil status (χ2 (3) 7.5, p = 0.06), scholarship (χ2 (4) 6.0, p = 0.2), and BMI (χ2 (3) 3.7, p = 0.3; Kendall Tau C = 0.04, p = 0.7). However, they differed in occupation (χ2 (7) 14.2, p = 0.04; V of Cramer = 0.4, p = 0.04). We also found a higher number of students in the MDS than in the LDS group. Additionally, the groups did not differ in age (U (p = 0.1).
3.3. Frequency of Food Consumption of the LDS and MDS Groups
When analyzing the food consumption of LDS and MDS group we found that the DS groups did not differ in the consumption of vegetables (χ2 (7) 9.4, p = 0.22), fruit (χ2 (7) 13.0, p = 0.07), white meat (χ2 (7) 6.3, p = 0.5), egg (χ2 (7) 10.9, p = 0.1), dairy products (χ2 (7) 8.6, p = 0.3), soft drinks (χ2 (7) 2.8, p = 0.9), and pasta (χ2 (7) 3.0, p = 0.09). However, they differed in their consumption of red meat (X2 (7) = 10.2, p = 0.02) and fast food (χ2 (4) = 33.8, p = 0.0001), and fatty foods: arepas (χ2 (4) 21.8, p = 0.001), fried food (χ2 (4) 33.85, p = 0.001), fritanga (χ2 (4) 11.5, p = 0.02), buñuelos (χ2 (4) 11.7, p = 0.02), cakes (χ2 (4) 14.5, p = 0.006), with a higher frequency of consumption in the MDS group than in the LDS group. Table 3 shows the frequency of consumption for all food groups.
Table 3.
Distribution of food groups in LDS and MDS.
3.4. Exploratory Predictors of the DS
The regression model (sum of squares = 2892.3; root mean square = 723.0; Effect size = 0.15; Standardized residual (Kolmogorov–Smirnov test, p = 0.2; homoscedastic) indicated that the consumption of some foods might be associated with the DS index. The supplements, such as Saccharomyces boulardii and white onion, were associated with a lower DS index. In comparison, the consumption of fatty foods and sesame may be linked to a higher DS index. These results matched previous analyses of food consumption frequency (See Table 4).
Table 4.
Food consumption predictors of the DS index.
4. Discussion
This study aimed to develop an exploratory instrument to link DS to medical records, sociodemographic variables, and dietary habits. Moreover, as expected, the frequency of food consumption was associated with the DS. However, we did not find medical records or sociodemographic variables as predictors. Therefore, our findings require an additional explanation.
4.1. Demographic and Anthropometric Data
As we expected, there were occupation differences between the LDS and MDS groups, as reported in previous studies [23,24]. The sample consisted of a higher number of students belonging to the MDS group, which matched prior studies reporting a positive correlation between higher education level and a higher prevalence of gastric disorders in Asian adults [23,24]. We suggest that our results may be explained by the fact that most students have a high level of education, which leads them to perceive their gastric condition differently. Moreover, students and workers with high responsibilities often have unhealthy lifestyles and dietary habits, which can lead to gastrointestinal disorders. Moreover, the occupational stress found in subjects with high educational levels could affect these disorders [25], which is also evident in our students, who belong to the MDS group.
On the other hand, contrary to Zhang et al.’s (2017) [24] findings, we did not find an association between DS and married status. From a socioeconomic perspective, married status could increase stress, responsibilities, and unhealthy dietary habits and increase the probability of suffering from DS. In the present study, most participants were single, which hampers our ability to examine any relationship between marital status and DS.
Differences in anthropometric data between the LDS and MDS groups were anticipated, as a previous study reported a strong association between underweight status and acute DS [26,27]. However, this association was not observed. The BMI distribution in the present sample may account for this finding, as most participants were of normal weight, and only seven were classified as underweight, which was insufficient to establish the previously reported relationship.
4.2. Frequency of Food Consumption and DS
Our results showed that food intake was associated with DS; specifically, the MDS group had higher intake of red meat, fast food, and fatty foods than the LDS group. These findings align with previous studies reporting associations between a higher DS index and higher red meat consumption [16,26], fast food [15], and fatty foods [3,5,7,10,15,26,27,28]. We suggest, as other studies have, that this type of food may negatively impact specific biological mechanisms involved in appetite regulation and digestion [7,26].
4.3. Exploratory Predictors of the DS
As expected, our results showed that high intake of fatty foods and sesame might predict higher DS, aligning with previous studies [3,5,7,10,15,26,27,29,30,31]. Fatty food seems to exacerbate symptoms such as fullness, bloating, nausea, and discomfort, enhancing sensitivity to gastric distension [3,5,10,14,27] and abnormalities in motility [27]. Prior studies have described at least two different mechanisms that might explain the association between fatty food intake and more severe DS found in this study: (1) high levels of cholecystokinin (CCK) and (2) the formation of acrolein. In the first mechanism, elevated circulating CCK levels have been associated with feelings of fullness or satiety [7]. Interestingly, CCK plays a crucial role in the symptoms of DS observed after consuming a meal rich in fat or protein. The CCK receptor antagonist dexloxiglumide seems to alleviate lipid-induced symptoms following intraduodenal lipid infusion in patients with DS [32]. In the second mechanism, when foods are fried at high temperatures, the cooking oil undergoes oxidation, resulting in the formation of acrolein. This pungent compound irritates the oral and nasal mucosa and contributes to the bitter taste of degraded oil, which may, in turn, contribute to the onset of postprandial fullness [5].
On the other hand, the adverse effects of sesame on DS may depend on the preparation method [31]. High-temperature processing of sesame can alter its phenolic compounds or the oxidation state of its fatty acids, potentially irritating the gastric mucosa in susceptible individuals [31] and activating their pro-inflammatory and pro-oxidant mechanisms [33].
Another interesting result was that a higher intake of Saccharomyces boulardii was associated with a lower DS index, which also warrants additional explanation. Saccharomyces boulardii’s effect on the DS index may be supported by its probiotic qualities, which have been widely recognized as beneficial for gastrointestinal health [34,35,36]. This supplement seems to modulate host immune responses, stabilizing intestinal epithelial barrier integrity, inhibiting pathogen binding, and promoting the secretion of digestive enzymes, thereby enhancing nutrient absorption and reducing inflammation [34,37].
The high intake of white onions was associated with a lower DS score. This fact may be explained by bioactive compounds such as quercetin, organosulfur compounds, and fructans, which have anti-inflammatory, antioxidant, and antimicrobial properties against pathogens such as H. pylori [38,39].
5. Conclusions
Changes in dietary habits can alleviate DS; however, because dietary habits differ across regions, their etiology will depend on participants’ age and occupations. Moreover, for this Colombian population, high intake of fatty foods and acidic foods might trigger a higher DS index. In contrast, consuming Saccharomyces boulardii probiotics will benefit gastrointestinal health.
6. Limitations
The present study has several inherent limitations. First, its cross-sectional design precludes the establishment of causal relationships or definitive conclusions regarding predictors of the DS index. Second, participants were not clinically evaluated by a physician; therefore, the presence of undiagnosed or comorbid medical conditions cannot be ruled out. In addition, the sample was recruited by convenience and was predominantly composed of students, which limits the external validity and generalizability of the findings. Furthermore, we did not assess 24 h dietary intake, eating behaviors (e.g., chewing speed, portion sizes, or meal skipping), levels of physical activity, fatigue, psychological factors (such as anxiety and stress), or sleep disorders. Consequently, the findings and interpretations of this study should be considered with caution.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/nu18020308/s1.
Author Contributions
R.C.-L., G.C.A.-C. and J.M.A.-C. contributed to the conception and design of this study, writing, review, and editing. J.M.A.-C., G.C.A.-C. and V.V.-P. organized the database and applied the survey. G.C.A.-C. and J.M.A.-C. contributed to the conception of methodology, formal analysis, and validation. L.B.-C., Y.O.S.-S., C.F.M.-d.l.P. and N.A.S.-L. reviewed, performed validation, and edited this manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This work was auspicated by Ciencia de Frontera-CONAHCYT: CF-2023-I-669, R.C.L., and by SECIHTI-Estancias Posdoctorales por México para la Formación y consolidación de las y los Investigadores por México, which awarded a postdoctoral fellowship to J.M.A.C.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki. The results are part of the protocol approved by the Benemérita Universidad Autónoma de Puebla, registration number 042, 16 April 2021.
Informed Consent Statement
Written informed consent has been obtained from the participants.
Data Availability Statement
The data are available at the following link: https://figshare.com/s/c493b54f673aaba71b27 (accessed on 14 January 2026).
Acknowledgments
We thank all investigators and participants in the study for their contributions. We are especially grateful to all the participants in this study and to José Manuel Gutiérrez Cortés for their technical support.
Conflicts of Interest
The authors declare no conflicts of interest, and the funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
Abbreviations
The following abbreviations are used in this manuscript:
| FD | Functional dyspepsia |
| DS | Dyspeptic symptoms |
| PDS | Postprandial distress syndrome |
| EPS | Epigastric pain syndrome |
| TNF | Tumor necrosis factor |
| PPIs | Proton pump inhibitors |
| NSAIDS | Nonsteroidal anti-inflammatory drugs |
| LDS | Less dyspeptic symptoms |
| MDS | More dyspeptic symptoms |
| UC | Ulcerative colitis |
Appendix A
Figure A1.
Regional distribution of the study in the Colombian population.
Appendix B
Table A1.
Self-administered survey directed to the Colombian Population.
References
- Lee, K.; Kwon, C.-i.; Yeniova, A.Ö.; Koyanagi, A.; Jacob, L.; Smith, L.; Lee, S.W.; Rahmati, M.; Shin, J.Y.; Shin, J.-I.; et al. Global Prevalence of Functional Dyspepsia According to Rome Criteria, 1990–2020: A Systematic Review and Meta-Analysis. Sci. Rep. 2024, 14, 4172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pesce, M.; Cargiolli, M.; Cassarano, S.; Polese, B.; De Conno, B.; Aurino, L.; Mancino, N.; Sarnelli, G. Diet and Functional Dyspepsia: Clinical Correlates and Therapeutic Perspectives. World J. Gastroenterol. 2020, 26, 456–465. [Google Scholar] [CrossRef] [Scilit]
- Pryor, J.; Burns, G.L.; Duncanson, K.; Horvat, J.C.; Walker, M.M.; Talley, N.J.; Keely, S. Functional Dyspepsia and Food: Immune Overlap with Food Sensitivity Disorders. Curr. Gastroenterol. Rep. 2020, 22, 51. [Google Scholar] [CrossRef] [Scilit]
- Shen, X.; Xie, A.; Li, Z.; Jiang, C.; Wu, J.; Li, M.; Yue, X. Research Progress for Probiotics Regulating Intestinal Flora to Improve Functional Dyspepsia: A Review. Foods 2024, 13, 151. [Google Scholar] [CrossRef] [Scilit]
- Colak, H.; Gunes, F.E.; Ozen Alahdab, Y.; Karakoyun, B. Investigation of Eating Habits in Patients with Functional Dyspepsia. Turk. J. Gastroenterol. 2022, 33, 673–681. [Google Scholar] [CrossRef] [Scilit]
- Vandenberghe, A.; Mion, F.; Allescher, H.D.; Roman, S.; Csiki, Z. Functional Dyspepsia: Still a Serious Challenge for Medical Practitioners and New Drug Investigators? A Belgian, French, German and Hungarian Opinion. Acta Gastroenterol. Belg. 2010, 73, 360–365. [Google Scholar] [PubMed]
- Amerikanou, C.; Kleftaki, S.-A.; Valsamidou, E.; Chroni, E.; Biagki, T.; Sigala, D.; Koutoulogenis, K.; Anapliotis, P.; Gioxari, A.; Kaliora, A.C. Food, Dietary Patterns, or Is Eating Behavior to Blame? Analyzing the Nutritional Aspects of Functional Dyspepsia. Nutrients 2023, 15, 1544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Popa, S.L.; Dumitrascu, D.I.; Pop, C.; Surdea-Blaga, T.; Ismaiel, A.; Chiarioni, G.; Dumitrascu, D.L.; Brata, V.D.; Grad, S. Exclusion Diets in Functional Dyspepsia. Nutrients 2022, 14, 2057. [Google Scholar] [CrossRef] [Scilit]
- Rettura, F.; Lambiase, C.; Grosso, A.; Rossi, A.; Tedeschi, R.; Ceccarelli, L.; Bellini, M. Role of Low-FODMAP Diet in Functional Dyspepsia: “Why”, “When”, and “to Whom”. Best Pract. Res. Clin. Gastroenterol. 2023, 62–63, 101831. [Google Scholar] [CrossRef] [Scilit]
- Volarić, M.; Šojat, D.; Majnarić, L.T.; Vučić, D. The Association between Functional Dyspepsia and Metabolic Syndrome—The State of the Art. Int. J. Environ. Res. Public Health 2024, 21, 237. [Google Scholar] [CrossRef] [Scilit]
- Oshima, T. Functional Dyspepsia: Current Understanding and Future Perspective. Digestion 2024, 105, 26–33. [Google Scholar] [CrossRef] [Scilit]
- Talley, N.J. Functional Dyspepsia: Advances in Diagnosis and Therapy. Gut Liver 2017, 11, 349–357. [Google Scholar] [CrossRef] [Scilit]
- Scarpellini, E.; Balsiger, L.M.; Broeders, B.; Houte, K.V.D.; Routhiaux, K.; Raymenants, K.; Carbone, F.; Tack, J. Nutrition and Disorders of Gut–Brain Interaction. Nutrients 2024, 16, 176. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharma, P.; Adhikari, S.; Katila, S.; Bajracharya, A.; Bohara, N.; Pathak, S.; Poudel, P.; Sapkota, P. Helicobacter Pylori Infection among Patients Undergoing Upper Gastrointestinal Endoscopy in a Tertiary Care Centre. J. Nepal Med. Assoc. 2024, 62, 5–8. [Google Scholar] [CrossRef] [Scilit]
- Agah, S.; Aminianfar, A.; Keshteli, A.H.; Bitarafan, V.; Adibi, P.; Esmaillzadeh, A.; Feinle-Bisset, C. Association between Dietary Macronutrient Intake and Symptoms in Uninvestigated Dyspepsia: Evidence from a Population-Based, Cross-Sectional Study. Nutrients 2022, 14, 2577. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akhondi-Meybodi, M.; Aghaei, M.A.; Hashemian, Z. The Role of Diet in the Management of Non-Ulcer Dyspepsia. Middle East J. Dig. Dis. 2015, 7, 19–24. [Google Scholar] [PubMed]
- Hu, M.L.; Rayner, C.K.; Wu, K.L.; Chuah, S.K.; Tai, W.C.; Chou, Y.P.; Chiu, Y.C.; Chiu, K.W.; Hu, T.H. Effect of Ginger on Gastric Motility and Symptoms of Functional Dyspepsia. World J. Gastroenterol. 2011, 17, 105–110. [Google Scholar] [CrossRef] [Scilit]
- Bordbar, G.; Miri, M.B.; Omidi, M.; Shoja, S.; Akhavan, M. Comparison of a Novel Herbal Medicine and Omeprazole in the Treatment of Functional Dyspepsia: A Randomized Double-Blinded Clinical Trial. Gastroenterol. Res. Pract. 2020, 2020, 5152736. [Google Scholar] [CrossRef] [Scilit]
- Ho, L.; Zhong, C.C.W.; Wong, C.H.L.; Wu, J.C.Y.; Chan, K.K.H.; Wu, I.X.Y.; Leung, T.H.; Chung, V.C.H. Chinese Herbal Medicine for Functional Dyspepsia: A Network Meta-Analysis of Prokinetic-Controlled Randomised Trials. Chin. Med. 2021, 16, 140. [Google Scholar] [CrossRef] [Scilit]
- Di Pierro, F.; Giovannone, M.; Saponara, M.; Ivaldi, L. Effectiveness of a Nutraceutical Supplement Containing Highly Standardized Perilla and Ginger Extracts in Patients with Functional Dyspepsia. Minerva Gastroenterol. Dietol. 2020, 66, 35–40. [Google Scholar] [CrossRef] [Scilit]
- Giacosa, A.; Guido, D.; Grassi, M.; Riva, A.; Morazzoni, P.; Bombardelli, E.; Perna, S.; Faliva, M.A.; Rondanelli, M. The Effect of Ginger (Zingiber Officinalis) and Artichoke (Cynara Cardunculus) Extract Supplementation on Functional Dyspepsia: A Randomised, Double-Blind, and Placebo-Controlled Clinical Trial. Evid.-Based Complement. Altern. Med. 2015, 2015, 915087. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dabos, K.J.; Sfika, E.; Vlatta, L.J.; Frantzi, D.; Amygdalos, G.I.; Giannikopoulos, G. Is Chios Mastic Gum Effective in the Treatment of Functional Dyspepsia? A Prospective Randomised Double-Blind Placebo Controlled Trial. J. Ethnopharmacol. 2010, 127, 205–209. [Google Scholar] [CrossRef] [Scilit]
- Sun, D.; Lei, L.; Xia, C.; Li, H.; Cao, M.; He, S.; Zhang, Z.; Guo, G.; Song, G.; Peng, J.; et al. Sociodemographic Disparities in Gastric Cancer and the Gastric Precancerous Cascade: A Population-Based Study. Lancet Reg. Health West. Pac 2022, 23, 100437. [Google Scholar] [CrossRef] [Scilit]
- Zhang, J.; Gan, L.; Wu, Z.; Yan, S.; Liu, X.; Guo, W. The Influence of Marital Status on the Stage at Diagnosis, Treatment, and Survival of Adult Patients with Gastric Cancer: A Population-Based Study. Oncotarget 2017, 8, 22385–22405. [Google Scholar] [CrossRef] [Scilit]
- Huerta-Franco, M.-R. Effects of Occupational Stress on the Gastrointestinal Tract. World J. Gastrointest. Pathophysiol. 2013, 4, 108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carmona-Sánchez, R.; Gómez-Escudero, O.; Zavala-Solares, M.; Bielsa-Fernández, M.V.; Coss-Adame, E.; Hernández-Guerrero, A.I.; Huerta-Iga, F.; Icaza-Chávez, M.E.; Lira-Pedrín, M.A.; Lizárraga-López, J.A.; et al. Consenso Mexicano Sobre La Dispepsia. Rev. Gastroenterol. Mex. 2017, 82, 309–327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carvalho, R.V.B.; Lorena, S.L.S.; de Souza Almeida, J.R.; Mesquita, M.A. Food Intolerance, Diet Composition, and Eating Patterns in Functional Dyspepsia Patients. Dig. Dis. Sci. 2010, 55, 60–65. [Google Scholar] [CrossRef] [Scilit]
- Pilichiewicz, A.N.; Horowitz, M.; Holtmann, G.J.; Talley, N.J.; Feinle-Bisset, C. Relationship Between Symptoms and Dietary Patterns in Patients with Functional Dyspepsia. Clin. Gastroenterol. Hepatol. 2009, 7, 317–322. [Google Scholar] [CrossRef] [Scilit]
- Oshima, T.; Okugawa, T.; Tomita, T.; Sakurai, J.; Toyoshima, F.; Watari, J.; Yamaguchi, K.; Fujimoto, K.; Adachi, K.; Kinoshita, Y.; et al. Generation of Dyspeptic Symptoms by Direct Acid and Water Infusion into the Stomachs of Functional Dyspepsia Patients and Healthy Subjects. Aliment. Pharmacol. Ther. 2012, 35, 175–182. [Google Scholar] [CrossRef] [Scilit]
- Abdeen, S.; Mathew, T.C.; Khan, I.; Dashti, H.; Asfar, S. Fasting-Induced Intestinal Damage Is Mediated by Oxidative and Inflammatory Responses. Br. J. Surg. 2009, 96, 552–559. [Google Scholar] [CrossRef] [Scilit]
- Khorrami, S.; Daneshmandi, S.; Mosayebi, G. Sesame Seeds Essential Oil and Sesamol Modulate the Pro-Inflammatory Function of Macrophages and Dendritic Cells and Promote Th2 Response. Med. J. Islam. Repub. Iran. 2018, 32, 566–573. [Google Scholar] [CrossRef] [Scilit]
- Chang, J.; Liu, Y.; Jiang, T.C.; Zhao, L.; Liu, J.W. Cholecystokinin and Cholecystokinin-A Receptor: An Attractive Treatment Strategy for Biliary Dyskinesia? World J. Gastroenterol. 2024, 30, 283–285. [Google Scholar] [CrossRef] [Scilit]
- Aggarwal, B.B.; Prasad, S.; Reuter, S.; Kannappan, R.; Yadav, V.R.; Park, B.; Hye Kim, J.; Gupta, S.C.; Phromnoi, K.; Sundaram, C.; et al. Identification of Novel Anti-Inflammatory Agents from Ayurvedic Medicine for Prevention of Chronic Diseases: Reverse Pharmacology; and Bedside to Bench Approach. Curr. Drug Targets 2011, 12, 1595–1653. [Google Scholar] [CrossRef] [Scilit]
- Kelesidis, T.; Pothoulakis, C. Efficacy and Safety of the Probiotic Saccharomyces boulardii for the Prevention and Therapy of Gastrointestinal Disorders. Ther. Adv. Gastroenterol. 2012, 5, 111–125. [Google Scholar] [CrossRef] [Scilit]
- Gareau, M.G.; Sherman, P.M.; Walker, W.A. Probiotics and the Gut Microbiota in Intestinal Health and Disease. Nat. Rev. Gastroenterol. Hepatol. 2010, 7, 503–514. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McFarland, L. V Systematic Review and Meta-Analysis of Saccharomyces boulardii in Adult Patients. World J. Gastroenterol. 2010, 16, 2202. [Google Scholar] [CrossRef] [Scilit]
- Czerucka, D.; Rampal, P. Diversity of Saccharomyces Boulardii CNCM I-745 Mechanisms of Action against Intestinal Infections. World J. Gastroenterol. 2019, 25, 2188–2203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, S.Y.; Lee, S.J.; Yim, D.G.; Hur, S.J. Changes in the Content and Bioavailability of Onion Quercetin and Grape Resveratrol During In Vitro Human Digestion. Foods 2020, 9, 694. [Google Scholar] [CrossRef] [Scilit]
- Aslam, Z.; Akhtar, S.; Imran, M.; Nadeem, M.; Gilani, S.; Elnashar, M.; Ahmed, E. Antioxidant Activity, Anti-Inflammatory Activities, Anti-Cancer and Chemical Composition of Spring Onion (Allium Fistolisum) Extracts. Res. J. Pharm. Biol. Chem. Sci. 2018, 8, 1880–1890. [Google Scholar]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.