


Abstract
Background and Objectives: Knee osteoarthritis (KOA) is a degenerative joint disease that affects quality of life through pain, impaired functional performance, and altered gait patterns. Hydrotherapy is a well-tolerated form of physical rehabilitation, especially suitable for patients with severe pain, as water’s properties support movement while reducing joint load. Its effects have been widely studied, primarily focusing on patient-reported outcomes, with limited synthesis of functional performance and gait-related outcomes. Materials and Methods: A systematic search was conducted in PubMed, Web of Science, Cochrane, PEDro, SpringerLink, ScienceDirect, and Google Scholar, following the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines. The search strategy included a combination of Medical Subject Headings (MeSH) terms and keywords. For example, the PubMed search strategy was as follows: (“knee osteoarthritis” OR “knee OA”) AND (“hydrotherapy” OR “aquatic therapy” OR “water-based exercise”) AND (“gait” OR “walking” OR “functional performance”). Randomized controlled trials (RCTs) from the last 10 years involving patients with KOA undergoing aquatic therapy were included. Primary outcomes included functional performance assessed by measures such as the 6 min walking test (6MWT), the Timed Up and Go (TUG) test, the five sit-to-stand (5 STS) and stair climb (SC) tests, and by using gait-related parameters (e.g., speed, cadence, and step length) assessed clinically or using technology. Patient-reported outcomes, including the Visual Analog Scale (VAS), Western Ontario and McMaster University’s Osteoarthritis Index (WOMAC), and Knee Injury and Osteoarthritis Outcome Score (KOOS), were analyzed as a secondary objective. Results: A total of 479 studies were identified, of which 13 met the eligibility criteria. The results revealed improvements in functional performance, with increases in 6MWT in five studies, the TUG test in four trials, and better performance in the 5-STS and SC tests in five studies. Benefits in gait parameters were noted in four studies. Additionally, one of the articles reported improvements in static and dynamic balance, another showed enhanced proprioception, and a third described more efficient muscle activation during gait following hydrotherapy. Consistent benefits in pain reduction, joint stiffness, and activities of daily living, as reflected by VAS, WOMAC, and KOOS, were also noted immediately and maintained at follow-up. The variability in outcome measures and intervention characteristics limited the possibility of data integration and the calculation of effect sizes. Conclusions: Hydrotherapy as a rehabilitation intervention may be associated with improvements in functional capacity, mobility, and self-reported physical ability in patients with KOA, with some evidence supporting a beneficial effect on gait; however, the certainty of evidence remains low to moderate due to heterogeneity among studies and limited sample sizes. These findings should be interpreted in light of the methodological limitations identified across the included trials.
1. Introduction
Knee osteoarthritis (KOA) is the most prevalent musculoskeletal disorder worldwide, affecting hundreds of millions of people. According to global estimates, approximately 374 million people were living with KOA in 2021, with over 30 million new cases each year and a substantial burden of more than 12 million disability-adjusted life years (DALYs). Females over 50 years of age and populations from regions with higher socio-demographic indices show increased risk. The disease affects adults and the elderly population, with an age-related increase in prevalence, leading to pain, functional limitations, and reduced quality of life (QoL) [1]. Impairments in walking ability and functional performance are the most disabling consequences for these patients, which is also demonstrated by gait analysis studies highlighting reduced physical performance in individuals with KOA [2,3].
Exercise-based rehabilitation is strongly recommended as a component of conservative management of KOA in international clinical guidelines, including those developed by the Osteoarthritis Research Society International (OARSI) [3]. However, land-based exercise programs may be poorly tolerated by some patients due to pain and functional limitations. In this context, the potential benefit of hydrotherapy is supported by biomechanical and physiological mechanisms, including reduced joint loading through buoyancy, increased muscular engagement due to water resistance, and enhanced proprioceptive feedback and circulation mediated by hydrostatic pressure, enabling safe and effective specific exercises for functional performance and gait [4].
Given that KOA directly affects walking ability and daily functional activities, the effects of rehabilitation interventions should be assessed using objective, validated outcome measures. Functional performance is commonly assessed through standardized tests, while computerized gait analysis allows detailed assessment of temporospatial, kinetic, kinematic, and neuromuscular parameters, providing valuable insights into mobility and movement strategies in patients with KOA [5]. Additionally, patient-reported outcome measures are widely used to evaluate pain, physical function, and health-related QoL. Current evidence indicates that systematic reviews on hydrotherapy in KOA [6] have primarily focused on pain reduction, self-reported physical function, and QoL [7]. Fewer studies have addressed balance, mobility, and postural control, while data on functional performance and walking-related outcomes remain limited and inconsistent [8]. Although several reviews suggest that hydrotherapy is comparable to land-based exercise in alleviating pain and improving physical function and QoL in patients with KOA in the short and long term, these findings are not entirely consistent. Variability in reported effects may be attributed to heterogeneity in study population, intervention protocols, and outcome measures, particularly in functional performance and gait-related outcomes. Compared with no intervention, hydrotherapy may improve daily activities and participation; however, its effects remain uncertain. While there is an association between better adherence, patient satisfaction, and a favorable safety profile, particularly for those with severe pain or a low tolerance for axial-loading exercises, it is unclear whether these advantages lead to better functional outcomes.
Although a growing number of studies have examined aquatic exercise in KOA, previous systematic reviews have primarily focused on patient-reported outcomes, including pain, stiffness, and perceived physical function. In contrast, less attention has been paid to objective measures of functional performance and gait-related parameters—the evidence being limited and fragmented—even though these are critical for maintaining mobility, independence, and overall daily functioning in this population. Recent RCTs have explored additional dimensions of walking ability—such as preferred walking speed, spatiotemporal gait variables, and aspects of neuromuscular control—that have not been synthesized across existing reviews. Therefore, this systematic review addresses this gap by offering a focused synthesis of objective functional performance and gait-related outcomes in patients with KOA, thereby extending the current evidence beyond previous meta-analyses.
Objective of the Review
The aim of this systematic review was to evaluate the effect of hydrotherapy compared with land-based exercises, education, usual care, conventional treatment, or no intervention on functional performance and gait-related outcomes (primary outcome) and patient-reported outcomes (secondary outcomes) in patients with KOA.
2. Materials and Methods
The methodology of this systematic review followed the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines [9], and the PRISMA checklist is provided in the Supplementary Materials (Table S1). It was designed to ensure adherence to standards of transparency and uniformity in data reporting and was prospectively registered in the International Prospective Register of Systematic Reviews (PROSPERO) [10] with registration number CRD420261297250. Minor refinements to the search strategy, such as the inclusion of additional synonyms, were performed to improve sensitivity.
2.1. Search Strategy
For this systematic review, an extensive search of articles in six databases (PubMed, Web of Science, Cochrane, PEDro, SpringerLink Journal, and ScienceDirect) was performed. Furthermore, Google Scholar was used as a supplementary source to identify additional relevant studies. To reduce selection bias, only the first 200 results sorted by relevance were screened. The search included studies published between January 2016 and February 2026. Only studies conducted in human participants and published in English were considered eligible.
The literature search followed the PICO (population, intervention, comparator, and outcome) framework.
The population of interest includes adults aged 40 and older diagnosed with KOA, according to the American College of Rheumatology criteria, with or without radiographic severity grading (Kellgren–Lawrence [3]).
The intervention consisted of hydrotherapy-based rehabilitation programs, including structured aquatic exercises (stretching, strength, balance, resistance training, free or treadmill walking, or dance-based exercises) performed in a therapeutic pool.
Comparators include land-based rehabilitation programs (e.g., exercise therapy, physiotherapy, and mud application), usual care, lifestyle-based interventions, regular treatment, educational programs, or no intervention.
The primary outcomes of interest were functional performance and gait-related parameters. Secondary outcomes included patient-reported measures of pain, physical function, and health-related quality of life. The review considered both functional performance tests and gait parameters as predefined outcomes. All of these variables were searched and extracted with equal methodological rigor according to the study protocol, following the results of standardized clinical tests, gait-related reported parameters [11,12,13,14,15,16,17,18], clinical outcome measures [19], and patient-reported functional scores [20,21,22,23,24,25,26].
The search strategy involved combining the following terms: “knee osteoarthritis”, “knee OA”, “gonarthrosis”, “hydrotherapy”, “aquatic exercise”, “aquatic therapy”, “water-based exercise”, “pool exercise”,” hydro-kinesiotherapy”, “gait”, “walking”, and “functional performance”. Boolean operators (“AND” and” OR”) were used to combine search terms. The search expression was adapted for each database as appropriate (Table 1).
Table 1.
Database search strategy.
Google Scholar was searched as a supplementary source. Due to the large number of results and the lack of advanced filtering options, only the first 200 results sorted by relevance were screened. This approach was adopted to maintain feasibility and reproducibility while minimizing selection bias, and all records were assessed using the predefined inclusion and exclusion criteria. The search was conducted by two evaluators who worked independently, with disagreements resolved by a third assessor. All references (479 in total) were imported into Zotero reference management software 9.0.3, where the records were archived and organized, and the duplicates were removed [27].
2.2. Study Selection
The selection of papers involved screening the titles and abstracts of the articles to determine eligibility based on the established inclusion and exclusion criteria and the PICO framework. Afterwards, the remaining articles were read in full to make the final selection. Inter-rater agreement statistics (e.g., Cohen’s kappa) between the two reviewers involved in this process were not calculated; however, disagreements during screening were minimal, and they were resolved through discussion with the third reviewer, who was consulted when necessary.
Inclusion criteria included the following:
- Randomized controlled trials (RCTs);
- Original studies involving patients with KOA over 40 years;
- KOA being clinically diagnosed using the American College of Rheumatology (ACR) criteria, without mandatory radiographic confirmation [28];
- Radiographic severity being assessed using the Kellgren–Laurence classification when reported [29];
- Studies comparing hydrotherapy with other rehabilitation interventions, usual care, educational programs, or no interventions;
- Studies assessing at least one standardized functional performance measure or one gait-related outcome (temporospatial, kinetic, or kinematic) before and after rehabilitation through hydrotherapy;
- English-language studies;
- Studies published between 2016 and 2026.
Exclusion criteria included the following:
- Studies involving children, adolescents, or adults under 40 years of age;
- Studies involving patients who underwent orthopedic surgery intervention on the lower limb or suffered from neurological diseases (central or peripheral);
- Studies that did not evaluate hydrotherapy as a rehabilitation intervention;
- Studies on non-human subjects.
2.3. Data Extraction
Two independent reviewers extracted data from the selected articles; any discrepancies were resolved through discussion until agreement was reached. Tables were created to include information such as the study’s authors, year of publication, number and characteristics of the population in the intervention and control groups, type and protocol of hydrotherapy as a rehabilitation treatment, the nature of the intervention in the control group, outcomes of interest (functional performance, gait-related parameters, and patient-reported outcomes), the methods and devices used, and the main findings. Data extraction was conducted using a standardized, predefined form that captured all of this information. Before the full data extraction, the form was tested on a small number of studies to ensure clarity and consistency.
2.4. Clinical and Functional Outcomes
2.4.1. Functional Performance Tests
Functional performance was assessed using several standardized tests. The 6 min walk test (6MWT) evaluates walking endurance and submaximal functional capacity [11,12], while the 10 m walk test (10MWT) measures gait speed and functional mobility [13]. The UKK 2 km assesses aerobic capacity and walking endurance [14]. Functional mobility was evaluated using the Timed Up and Go (TUG) test [15] and the sit-to-stand (STS) test, the latter of which reflects lower-limb strength and performance [16]. The 5STS offers a practical, simple method for evaluating lower-limb performance in older adults and serves as an alternative assessment for identifying community-dwelling older adults with reduced gait speed when direct gait evaluation is not feasible. The study further suggests specific cutoff values for 5STS based on gait speeds below 0.8 m/s for women and below 1.0 m/s for men [17]. Walking speed and mobility were further assessed with the 40 m fast-paced walk test (FPWT-40). Stair negotiation ability was evaluated using the stair climb test (SCT) and stair test (ST), which measure functional mobility during stair ascent and/or descent [18]. The comprehensive descriptions of each test are provided in the Supplementary Materials (Table S2).
2.4.2. Gait-Related Outcome
Gait-related outcomes were predefined as primary outcomes and were included when reported in the eligible studies. These comprised spatiotemporal parameters (step length, stride length, cadence, walking speed, and gait cycle phases), kinematic variables (knee flexion–extension angles and range of motion), and kinetic measures (knee adduction moment [KAM], KAM impulse, and ground reaction forces [GRF]). Additional gait-related variables, such as symmetry, variability, posture, and muscle activation during gait, were considered exploratory outcomes due to heterogeneous reporting across studies. All gait data were extracted as reported in the individual studies, irrespective of the measurement instrument used.
2.4.3. Clinical Outcome Measures
In KOA, joint function can be affected by factors such as knee flexor and extensor muscle strength, joint range of motion (ROM), and circumferences of the lower limb (thigh, knee, and calf). These parameters, along with local pain, influence functional capacity and are important in evaluating knee function [19].
2.4.4. Patient-Reported Functional Outcomes
In KOA research, the patient-reported functional outcomes are assessed using standardized tools, which include pain scales such as the Visual Analog Scale (VAS) [20] and Numeric Rating Scale (NRS) [21], disease-specific questionnaires like Western Ontario and McMaster University’s Osteoarthritis Index (WOMAC) [22] and Knee Injury and Osteoarthritis Outcome Score (KOOS) [23] and outcome measures such as the Short Form-36 [23,24], EuroQol-5D [25] and health assessment questionnaire disability index (HAQ-DI) [26].
2.5. Quality Assessment
The methodological quality of the included studies was assessed using the revised Cochrane risk of bias tool for randomized trials (RoB2), designed for systematic reviews, which assesses five standardized domains [30]. Two reviewers independently assessed each RCT. The results were then compared, and any discrepancies were re-evaluated through discussion. In cases where consensus could not be reached, the third reviewer was consulted. The evaluation was conducted at the outcome level, focusing specifically on functional performance outcomes and gait-related parameters. In addition, the overall certainty of the evidence was determined using the GRADE (Grading of Recommendations Assessment, Development and Evaluation) approach [31]. All included studies were RCTs, corresponding to Level 1 evidence according to the Oxford Center for Evidence-Based Medicine; therefore, additional classifications were not considered necessary.
2.6. Statistical Analysis
The analysis was mainly descriptive. A structured meta-analysis was not conducted because of methodological heterogeneity in the interventions and in the functional and gait parameters assessed across the included studies. The number of studies measuring the same outcome was too small to support meaningful subgroup meta-analyses. A qualitative synthesis of the selected studies was conducted, focusing on population characteristics, interventions, control groups, and outcomes assessed.
3. Results
3.1. Search Results
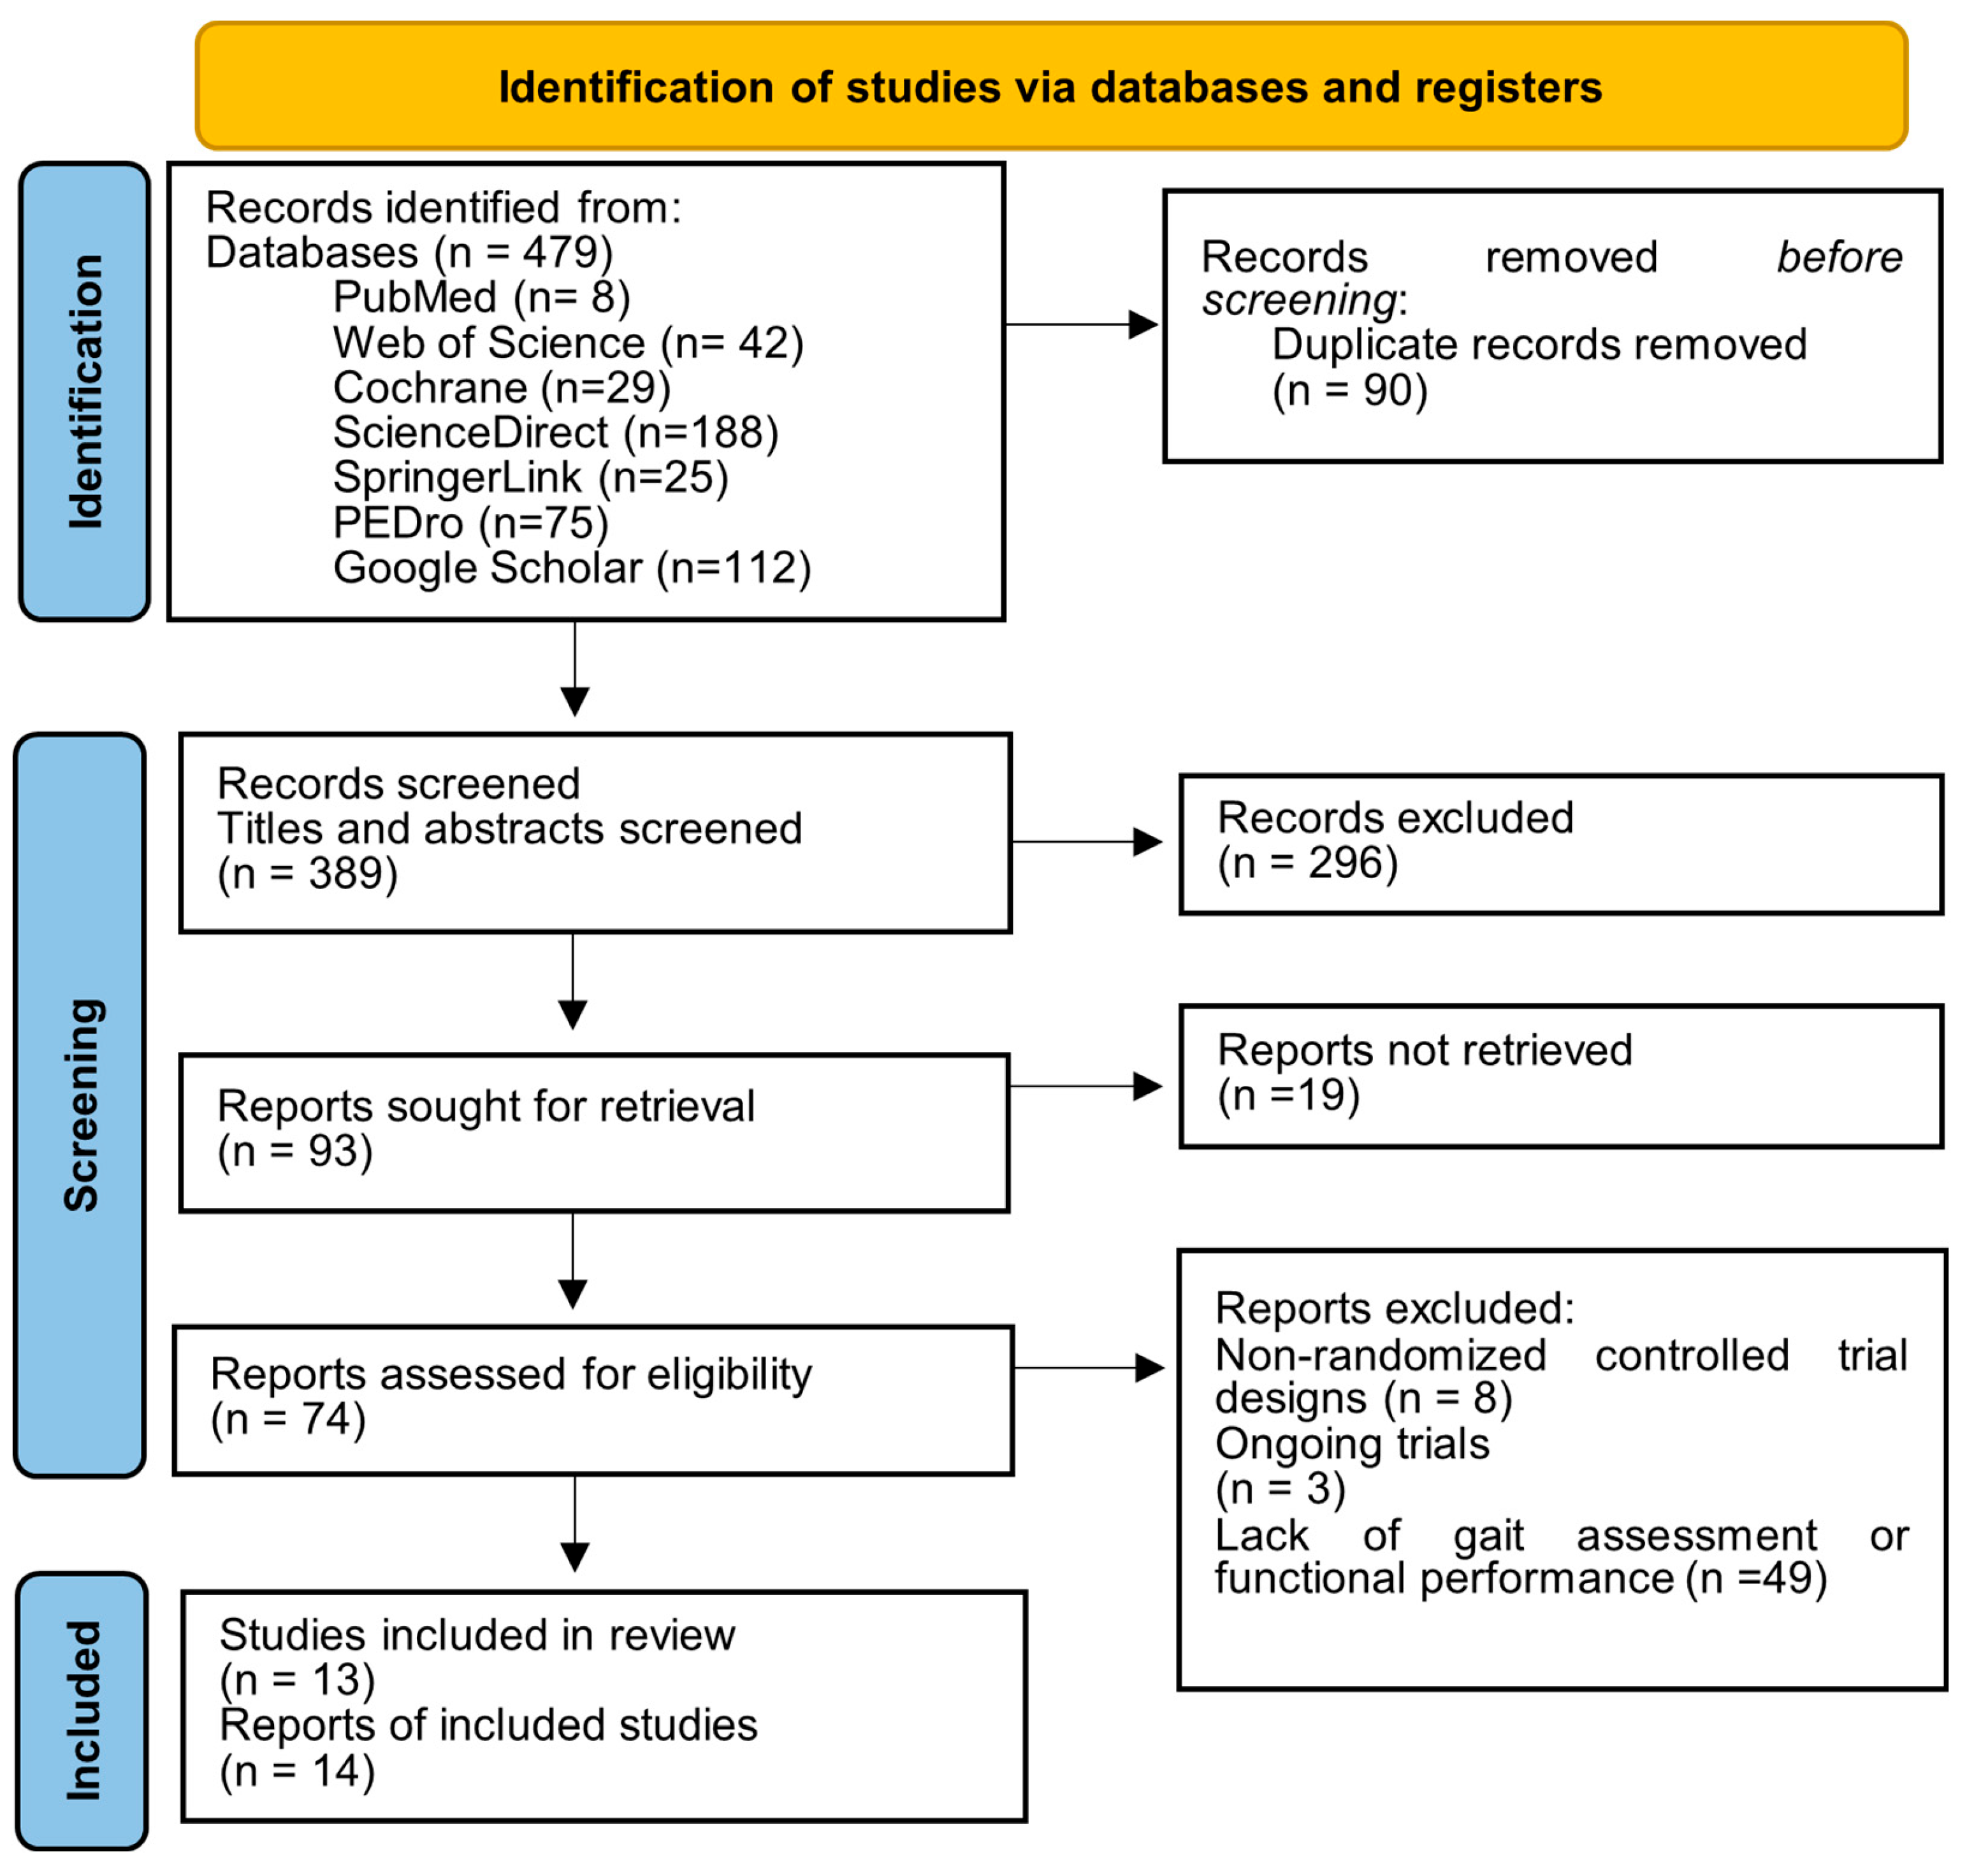
The initial database search identified 479 records. After removing duplicate records, 389 articles remained. Screening of titles and abstracts resulted in the exclusion of 296 studies for the following reasons: studies not addressing KOA (n = 38), studies involving surgical interventions (n = 36), absence of hydrotherapy as a rehabilitation intervention (n = 72), conference abstracts (n = 12), or publications not representing original research (n = 138).
The full texts of 93 potentially relevant articles were evaluated for eligibility; however, 19 could not be retrieved. Consequently, 74 full-text articles were evaluated in detail in accordance with the predefined inclusion and exclusion criteria. Of these, 61 studies were excluded due to non-randomized controlled trial designs (n = 8), ongoing trials (n = 3), and the lack of gait assessment or functional performance measurement (n = 49). Two publications were identified as reporting results from the same clinical trial; therefore, data were extracted from the most complete and recent report to avoid double-counting. A total of 13 studies (reported in 14 publications) met the eligibility criteria and were included in the final qualitative synthesis (Figure 1).
Figure 1.
PRISMA flow diagram. Source: [9].
The findings are reported according to the predefined primary outcomes—functional performance tests and gait-related parameters—and secondary outcomes, comprising patient-reported measures of pain, physical function, and health-related quality of life. All studies reported functional performance test results and gait-related outcomes; only two studies did not report patients’ self-reported outcomes.
3.2. Characteristics of Included Studies
The studies were evaluated, and the data were extracted and recorded in specific tables. The author’s names, country, number of participants in the intervention and control groups, age, body mass index (BMI), and Kellgren–Laurence (K-L) stage, when reported, were noted (Table 2).
Table 2.
Characteristics of study groups.
The 13 included RCTs were conducted across diverse geographical areas, including Spain, Finland, Brazil, Thailand, Iran, Lithuania, and India, with sample sizes ranging from 16 to 290 participants. Most studies involved adults of middle age and older, though some focused on more specific populations, such as postmenopausal women and the elderly, leading to variability in baseline characteristics. A critical comparison of protocols reveals substantial heterogeneity. The duration of aqua therapy programs varied from two to seven sessions per week, with a maximum of 24 sessions delivered over periods ranging from ten days to twelve weeks. The type and intensity of aquatic interventions differed across the studies, including aquatic resistance training, walking exercises, stretching, balance training, and combined programs, reflecting a lack of standardization in exercise design. Moreover, hydrotherapy was evaluated against different control conditions, such as land-based exercises and physiotherapy, mud application, usual care or medication, education, lifestyle, or no intervention. The follow-up periods varied between 1 and 6 months. These differences in experimental and control group interventions and follow-up duration may have influenced the reported outcomes and direct comparability between studies. Another source of heterogeneity was the different reported outcome measures across studies. We grouped the studies, and only a limited number of comparable outcomes (six for the 6MWT and three for the TUG test) were reported. As a result, a quantitative synthesis was conducted.
The description of the intervention in the two groups, the time of application, the outcome, a summary of the results, and the reference number were recorded for each study (Table 3).
Table 3.
Summary of the included studies.
3.3. Risk of Bias
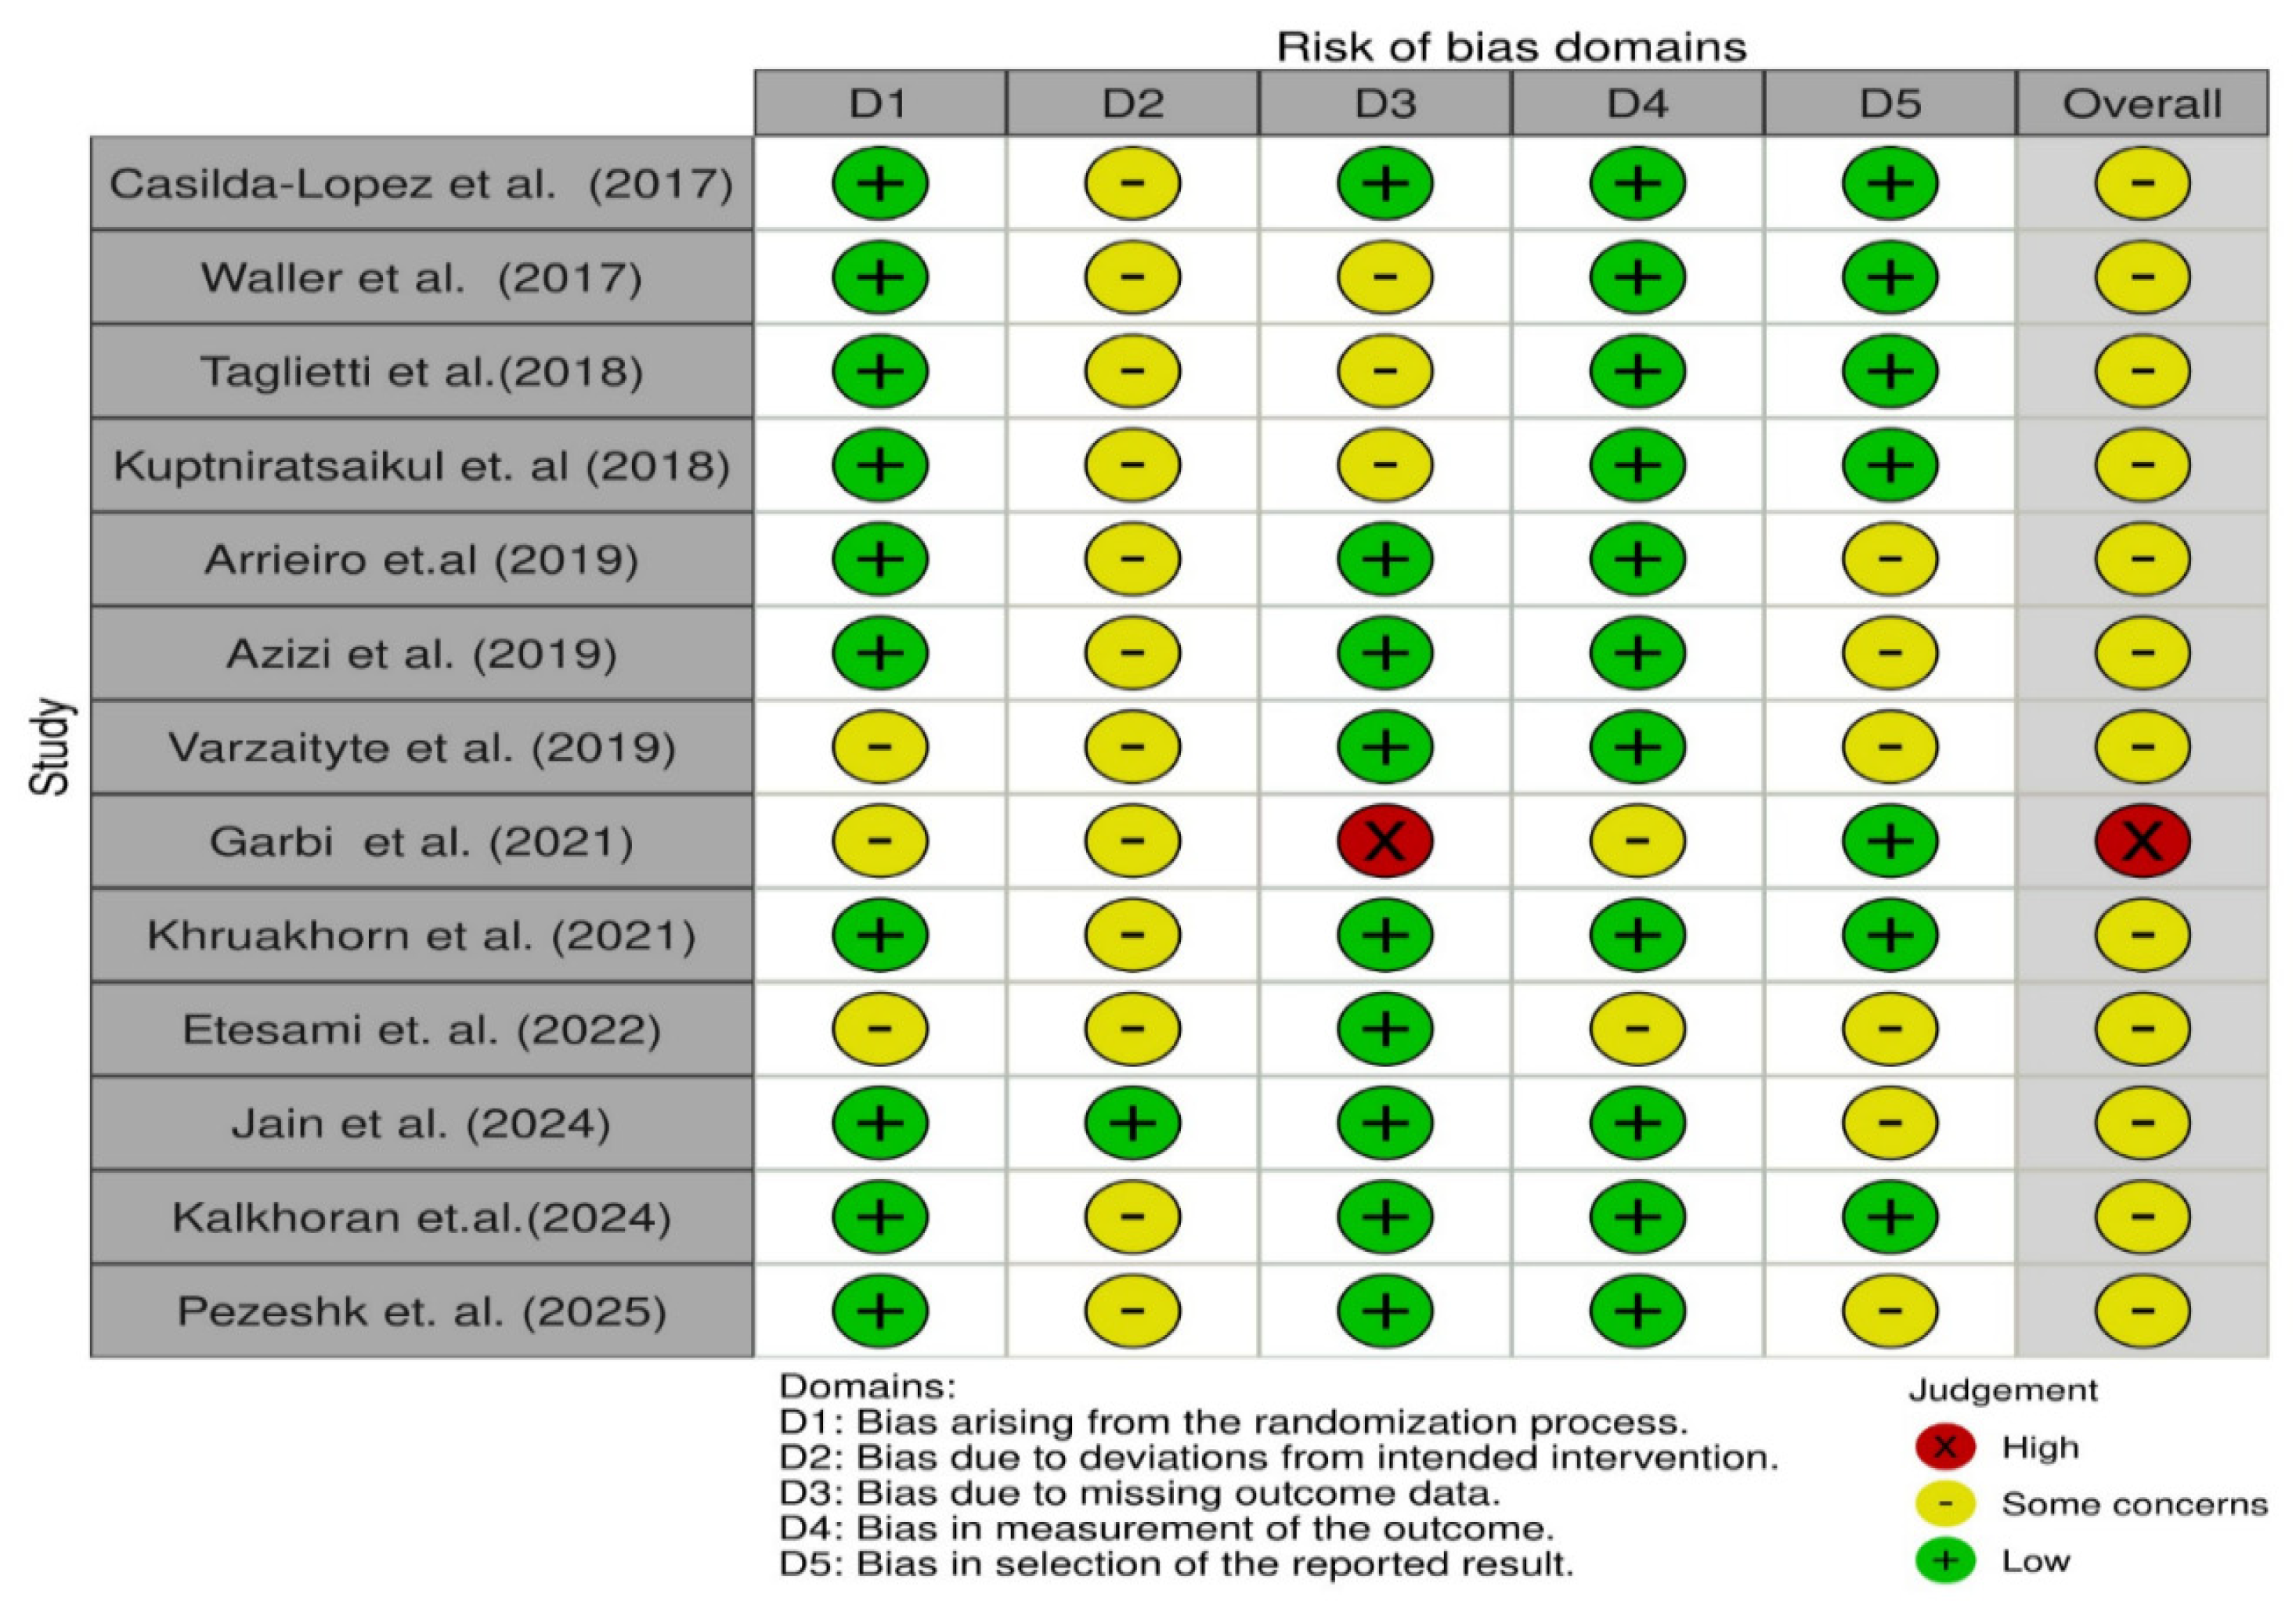
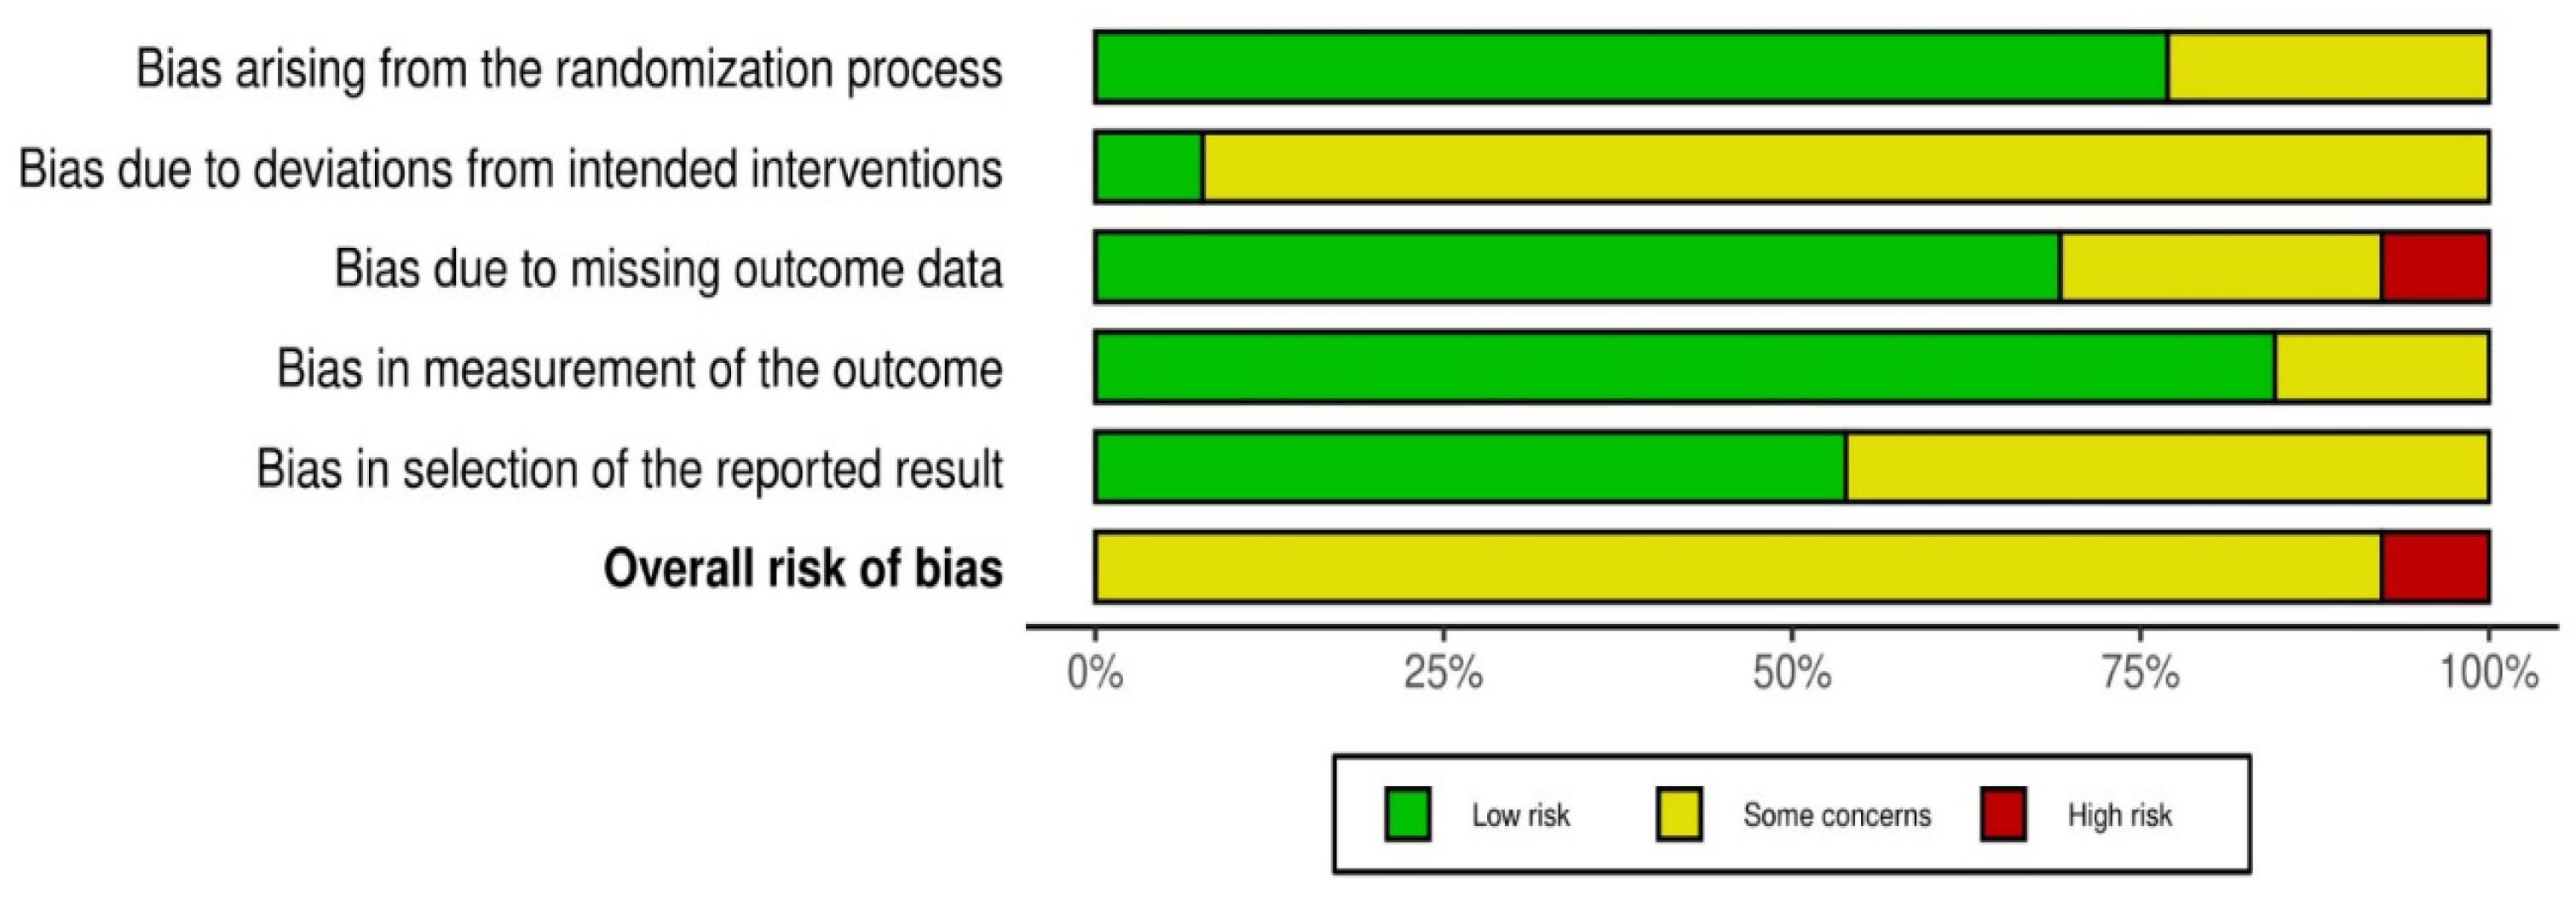
The overall risk of bias across the included studies was assessed as exhibiting “some concerns”. The RoB2 tool evaluated five domains: bias arising from the randomization process, bias due to deviations from intended interventions, bias due to missing outcome data, bias in measurement of the outcome, and bias in selection of the reported result [29,30]. Domains D1 (randomization) and D4 (outcome measurement) were judged as low risk in the majority of trials. However, several studies raised concerns in domains D2 (deviations from intended interventions) and D5 (selection of reported results), which have direct implications for the interpretation of patient-reported outcomes such as WOMAC and VAS scores, as these measures are more susceptible to performance and expectation bias. Performance-based tests (e.g., TUG and 6MWT) and gait-related parameters are inherently less influenced by subjective factors and were therefore considered more robust to these sources of bias. Only one study was rated at high risk, primarily due to concerns regarding missing outcome data (D3). These considerations were taken into account in the interpretation of the findings (Figure 2).
Figure 2.
Risk of bias using RoB2 for included studies [32,33,34,35,36,37,38,39,40,41,42,43,44].
In rehabilitation research, blinding of participants and therapists is often difficult to achieve due to the nature of exercise-based interventions. In the included trials, both aquatic and land-based exercise programs required active participation and supervision, rendering blinding impractical and potentially increasing the risk of performance bias. In addition, patient-reported outcomes such as pain or perceived physical function may be more susceptible to expectation or performance bias, whereas performance-based tests and gait-related parameters are generally considered less influenced by subjective factors.
Although the included trials were generally conducted in accordance with standard RCT design principles, the methodological quality was variable. Several studies exhibited concerns related to blinding of participants and care providers—an inherent limitation of exercise-based rehabilitation research—as well as incomplete outcome data and selective reporting. These limitations should be considered when interpreting the magnitude and consistency of the reported effects. A graphical summary of the risk of bias assessment is shown in Figure 2 and Figure 3.
Figure 3.
A summary plot of RoB2 for the included studies [32,33,34,35,36,37,38,39,40,41,42,43,44].
Given the methodological heterogeneity of the included studies, detailed study-specific data are presented in Table 3. The following sections provide a narrative synthesis of the results by outcome domain, including functional performance, gait-related parameters, and patient-reported outcomes.
3.4. Functional Performance Outcomes
Functional performance outcomes were evaluated in eleven of the included RCTs [32,33,34,35,36,38,39,40,41,42,43]. Improvements in the 6 min walk test (6MWT) were reported in five studies [32,35,36,39,41] with statistically significant between-group differences in favor of hydrotherapy observed in the study of Casilda et al. [32]. The Timed Up and Go (TUG) test was assessed in five studies [34,39,40,41,42], with significant improvements in the intervention group relative to controls reported in Garbi et al. and Jain et al. [39,42]. Improvements in the five times sit-to-stand (5STS) test were documented in two studies [38,40]. Varzatyte et al. noted statistical significance after mineral bath water therapy compared with the control group [38]. The stair climb test (SCT) showed significant within-group changes in the trials of Etesami et al. following 8 weeks of hydrokinetotherapy and Khruakhorn et al. after six weeks of water-based stretching exercises; the latter observed significant statistical improvement between groups [40,41]. Gait speed was clinically assessed using tools such as the UKK 2 km test and 10 m walk test in three studies [33,38,43]. In the trial of Varzaityte et al., the specific testing protocol was not described in detail in the published methodology [38]. The improvement was statistically significant in the interventional groups compared to the controls at the end of treatment, but it was not maintained at follow-up [33,38].
Overall, most studies reported improvements in functional performance following hydrotherapy intervention.
3.5. Gait-Related Outcomes
Gait-related parameters were evaluated using technology in two of the included RCTs [37,44], which substantially limits the strength and generalizability of any conclusions regarding the effects of hydrotherapy on walking mechanics. An additional three studies assessed walking speed using previously described clinical functional performance tests [33,38,43].
Azizi et al. investigated the effects of an 8-week aquatic exercise program in elderly men with KOA compared with a control group receiving lifestyle advice evaluating temporospatial gait parameters and balance measures [37]. Significant improvements were observed in stride length and cadence in the interventional group, while no significant changes were noted in step time or step width compared with the control group. Static and dynamic balance also improved significantly in the hydrotherapy group. Pezeshk et al. (2025) compared aqua therapy and land-based exercise over 8 weeks, finding that although both exercise modalities were beneficial, hydrotherapy produced greater biomechanical and neuromuscular improvements [44]. The hydrotherapy group showed significant improvement in knee range of motion during early stance, rectus femoris activity, and overall muscle activation, with moderate-to-large effect sizes. Compared with the land-based exercise group, hydrotherapy demonstrated larger effect sizes for knee ROM improvement, as well as greater enhancement of rectus femoris activation and reduction in hamstring activity, indicating superior optimization of muscle activation patterns during the early stance phase of gait.
While the available data suggest potential benefits in selected gait parameters—including walking speed, stride length, and cadence—the findings should be interpreted with considerable caution, given the small number of contributing studies, the heterogeneity in assessment methods, and the variability in reported outcomes.
3.6. Patient-Reported Functional Outcomes
Patient-reported outcomes were assessed in eleven of the included RCTs [32,33,34,35,36,37,38,39,40,42,44]. These outcomes were evaluated using validated instruments commonly applied in KOA research, including the NRS, VAS, WOMAC, KOOS, and SF-36 questionnaires.
WOMAC score was assessed in six studies, all of which showed improvements in both groups [32,34,36,39,40,42]. Statistically significant differences between interventional and control groups were noted in five studies [32,34,39,40,42]. In Casilda et al.’s study, the improvement was noted only in pain and total domains of WOMAC [32].
KOOS was assessed in two studies [33,44]. In Waller et al.’s research, no improvement was observed [33], and Pezeshk et al. in 2025 showed that the KOOS increased in both groups, with a large effect size observed in the water-exercise group, although the difference was not statistically significant [44].
The VAS scale was used in four studies [34,37,38,42] and the NRS in one study [35]. Across all trials, pain levels decreased in both groups with a statistically significant improvement in the interventional group [34,35,37,38,42].
SF-33 was evaluated in three studies, showing increased scores but no differences between groups [34,36,38].
Quality of life, as measured by the WHOQOL-100, was evaluated in one study using a specific questionnaire. QOL outcomes showed improvements in both groups at 6 weeks, with significant gains in the physical domain and in the total score in both the intervention and control groups. Additionally, the hydrotherapy group showed improvement in the environmental domain. At 6 months, only the hydrotherapy group showed sustained, significant improvements in mental and social quality-of-life scores and overall quality-of-life scores [40].
3.7. Certainty of Evidence (GRADE Assessment)
The certainty of evidence for the main outcomes was evaluated using the Grading of Recommendations Assessment, Development and Evaluation (GRADE) approach. The evaluation considered the domains of risk of bias, inconsistency, indirectness, imprecision, and publication bias. Downgrading decisions were operationalized as follows: for functional performance outcomes, the certainty was downgraded one level for imprecision, owing to small sample sizes in several trials and limited overlap in the specific tests used (e.g., TUG, 6MWT, and STS), resulting in moderate certainty. For gait-related outcomes, the certainty was downgraded two levels—one for serious inconsistency, reflecting substantial variability in the parameters assessed (walking speed, cadence, and stride length) and the methodological diversity of assessment instruments, and one for serious imprecision, due to the small number of contributing studies and limited sample sizes, resulting in low certainty. For patient-reported outcomes, the certainty was similarly downgraded two levels—one for serious inconsistency, attributable to the use of different validated instruments (WOMAC, KOOS, VAS, and SF-36) with distinct scoring systems and domains, and one for serious imprecision, resulting in low certainty overall. The detailed results of the GRADE assessment are presented in Table 4.
Table 4.
GRADE assessment.
4. Discussion
The findings of the present review suggest that hydrotherapy may contribute to clinically meaningful improvements in functional mobility, walking capacity, and pain in patients with KOA. Locomotor performance gains were reflected by increased distance in 6MWT [32,35,36,39,41], improved TUG performance [34,39,40,41,42], enhanced walking speed [33,38,43], and better performance in SCT and STS tests. However, it is equally important to acknowledge that several trials did not demonstrate statistically significant between-group differences. Taglietti et al. (2018) reported no significant improvement in TUG performance in either the aquatic exercise or patient education group [34]. Kuptniratsaikul et al. (2018) found no significant differences between underwater treadmill and home exercise programs for the 6MWT improvement at four weeks [35]. Similarly, Arrieriro et al. (2019) and Etesami et al. (2022) reported comparable improvements in both aquatic and land-based groups across multiple functional outcomes, with no statistically significant between-group differences [36,41]. These null results are clinically relevant and suggest that the benefits of hydrotherapy, while present, are not consistently superior to other rehabilitation modalities and may be partly attributable to the general effects of structured exercise participation.
Improvements in static and dynamic balance, enhanced proprioception, and optimized muscle activation during gait were reported in a subset of trials; however, the amplitude of these improvements varied across studies, reflecting differences in intervention protocols, treatment duration, and patient characteristics. Aquatic therapy demonstrated beneficial effects on pain reduction, decreased joint stiffness, functional improvement, and activities of daily living, as measured by VAS, WOMAC, and KOOS, representing the most consistent finding across the included studies. These benefits were observed immediately after the intervention and, in some studies, were maintained at follow-up for up to three months [32,34] and up to six months [40]. Casilda et al. (2017) additionally reported increased cardiorespiratory capacity, reduced post-exercise heart rate, and decreased fatigue following aquatic interventions, suggesting systemic benefits beyond joint-related outcomes [32]. Waller et al. noted that aquatic resistance training has been associated with favorable changes in body composition, including reductions in fat mass and overall improvements, which are clinically relevant, as excess adiposity is known to contribute to KOA progression through both increased mechanical joint loading and low-grade inflammatory processes [33,45].
The observation that several studies reported outcomes in aquatic therapy comparable to those achieved with patient education or matched land-based exercise warrants critical reflection [34,36]. While this may suggest that structured physical activity, irrespective of the medium, is a primary driver of functional improvement, it does not diminish the specific value of the aquatic environment. The therapeutic mechanisms of hydrotherapy are likely multifactorial: buoyancy provides unloading of joints, hydrostatic pressure reduces periarticular edema, and thermal effects contribute to analgesia and muscle relaxation—properties that enable exercise participation in patients who would otherwise not tolerate land-based programs [4].
The RCT of Varzaityte et al. (2019) further illustrated this point: balneological intervention combining mineral sodium chloride baths or peloid therapy with physiotherapy produced significantly greater improvements in walking speed, 5TST performance, knee flexion range, and lower-limb muscle strength compared with physiotherapy alone, with sustained benefits at one-month follow-up [38]. The absence of significant differences between mineral baths and mud applications may indicate a shared therapeutic mechanism related to the thermal and mechanical properties of natural factors in this context [46,47,48].
These findings are broadly consistent with those of previously published systematic reviews and meta-analyses. Ma et al. (2022) reported significant improvements in WOMAC pain, knee extensor muscle strength, and TUG performance following aquatic physical therapy compared with no intervention, with no significant differences observed in quality of life, flexibility, or most functional outcomes [7]. The meta-analysis by Lei et al. focused on the effects of hydrotherapy versus physiotherapy on pain relief, patient-reported outcomes such as WOMAC and the Short Form 12 Health Survey, and side effects. All of these outcomes showed significant improvement in the IG at 1, 14, and 8 weeks, with no additional adverse effects [48]. Xu et al. (2022), analyzing 22 RCTs, showed improved pain relief (maintained at 3 months), stiffness, and physical function compared with no exercise, yet revealed no significant differences when compared with land-based exercise programs, and also no negative outcomes [49]. More recent evidence from Valenzuela-Fuenzalida et al. (2024) confirms significant improvements in WOMAC stiffness, pain intensity VAS score, and TUG in favor of aquatic exercise, while WOMAC pain, physical function, and KOOS outcomes showed no statistically significant superiority over other therapeutic modalities [50]. Analyzing eight RCTs of patient-reported outcomes (KOOS, VAS, and WOMAC), Dong et al. (2018) conducted a meta-analysis that indicated no significant differences between aquatic exercise and land-based exercise in pain reduction, physical function, or quality of life in patients with KOA for both short- and long-term interventions [6]. In the review by Noor et al. (2023), improvements in functional performance measures—including TUG, 6MWT, STS, and SCT—were reported following aquatic therapy [8], consistent with the present findings. Unlike previous reviews, the present study specifically targeted functional performance and gait-related outcomes, incorporating recent RCTs examining neuro-muscular control, proprioception, and range of motion, thereby extending the available evidence.
Taken together, these findings involve several clinical implications for the rehabilitation of patients with KOA. The disease’s association with significant impairments in gait and functional performance, including reduced walking speed, shorter step length, and altered loading patterns [51,52,53,54], suggest that these impairments may be partially addressed through hydrotherapy-based rehabilitation. The aquatic environment offers specific clinical advantages by reducing loading while allowing safe performance of strengthening and gait-related exercises [4], thereby facilitating participation in patients with moderate to severe pain, elevated BMI, or kinesiophobia. Nevertheless, the results of this review do not demonstrate consistent superiority of hydrotherapy over land-based exercises. Studies comparing aquatic with land-based exercises in patients with KOA generally reported improvements in pain, functional performance, and walking capacity [35,36,40,41]. Jain et al. (2024) and Pezeshk et al. (2025) observed benefits in both interventions, with slightly greater functional and neuromuscular improvements following hydrotherapy [42,44]. A combined rehabilitation approach integrating early aquatic therapy with progressive land-based training may be more effective in optimizing long-term functional outcomes and adherence. These findings suggest that hydrotherapy should be considered a complementary component within a comprehensive rehabilitation program rather than an isolated intervention, with careful patient selection based on clinical characteristics and contraindications. Moreover, aquatic therapy is a cost-effective adjunct therapy for KOA, offering a favorable balance between costs and benefits, and it is a recommended option in modern disease management [55].
Several limitations of this review should be acknowledged when interpreting the findings. The included trials exhibited substantial methodological heterogeneity across multiple dimensions, including the type, intensity, frequency, and duration of aquatic interventions; water temperature; pool depth; and the degree of therapist supervision, precluding direct protocol comparison and possibly contributing meaningfully to the variability in reported outcomes. Sample sizes across the included studies ranged from 16 to 290 participants, and the majority of trials enrolled fewer than 60 participants, which raises concerns regarding statistical power and the precision of effect estimates. Several studies did not report radiographic disease severity according to the Kellgren–Lawrence classification [29], limiting the ability to assess whether treatment responses differed across disease stages. A subset of trials did not provide detailed baseline demographic characteristics, further constraining the interpretation of subgroup-specific findings.
The absence of participant and therapist blinding—an inherent constraint of exercise-based rehabilitation research—represents an additional source of potential performance and detection bias, particularly for patient-reported outcomes such as pain intensity and perceived functional capacity, which are more susceptible to the expectation effect than objective performance-based tests. Furthermore, only a limited number of studies assessed gait-related parameters using biomechanical instrumentation; the remainder relied on clinical walking tests, which, while validated and widely used, do not capture the full complexity of gait mechanics in individuals with KOA. The heterogeneity of comparator interventions—ranging from no treatment and usual care to structured land-based rehabilitation programs—introduces further variability that limits the interpretability of between-group effect sizes across studies.
A further limitation of this review is the inability to conclude sex-based differences in response to hydrotherapy. Several included trials enrolled exclusively female populations, predominantly postmenopausal women [32,33,36,41,43,44], while mixed-sex trials did not consistently report sex-stratified outcome data [34,35,38,39,40,42]. Given the higher prevalence of KOA in women, documented sex differences in pain processing and neuromuscular function, and the potential for hormonal factors to modulate responses to aquatic exercise, future research should prioritize adequately powered trials with pre-specified subgroup analyses by sex.
The included trials were conducted across seven countries representing diverse geographical, cultural, and healthcare contexts. While this geographical breadth enhances the generalizability of the review’s findings, it also introduces potential sources of heterogeneity that are difficult to disentangle from other methodological sources of variability. Differences in population-level characteristics—including baseline BMI, radiographic disease severity, habitual physical activity levels, and access to rehabilitation services—may have differentially influenced treatment responses across study settings. Direct cross-cultural comparisons of treatment efficacy were not feasible within the current design. Future systematic reviews and primary trials should consider cultural and population-level factors as pre-specified moderators of treatment response in aquatic rehabilitation for KOA.
Outcome heterogeneity represents a major methodological limitation of this review. Across the included trials, functional performance was assessed using a wide variety of instruments—including the 6MWT, TUG, 5STS, 2KK, and 10MWT—while gait-related parameters encompassed temporospatial variables, kinematic and kinetic measures, and, when available, neuromuscular indices assessed using markedly different methodologies. Patient-reported outcomes similarly varied, with studies employing WOMAC, KOOS, VAS, NRS, and SF-36, each capturing overlapping yet distinct constructs. This diversity of measurement approaches prevented the pooling of data across studies and limited the direct comparability of results. To improve interpretive clarity, outcomes in this review were organized into three predefined domains—functional performance, gait-related parameters, and patient-reported functional outcomes—consistent with the structure of the GRADE assessment (Table 4). The absence of a universally adopted core outcome set for aquatic rehabilitation in KOA is a recognized gap in the field; adoption of standardized outcome measures, such as those recommended by OARSI [18], would substantially facilitate evidence synthesis in future systematic reviews and meta-analyses.
This review has several methodological strengths that should be acknowledged alongside its limitations. The restriction to RCTs reduces the risks of confounding inherent to observational designs and focuses on a single joint condition—knee osteoarthritis—which reduces clinical heterogeneity relative to reviews examining mixed osteoarthritis populations, allowing for a more condition-specific interpretation of findings. The systematic search strategy across seven databases, combined with independent dual-reviewer screening, data extraction, and risk of bias assessment using the RoB2 tool, adhered to PRISMA guidelines and enhanced the reproducibility of the review process. However, these procedural strengths must be interpreted in the context of the moderate-to-low certainty of evidence, as determined by GRADE, which limits the strength of any recommendations that can be derived from these findings.
Future research should prioritize standardized aquatic exercise protocols defining optimal frequency, intensity, duration, water temperature, and type of aquatic intervention for patients with KOA. Well-designed RCTs with larger sample sizes and longer follow-up periods and instrumented gait analysis are needed to evaluate the long-term effectiveness and sustainability of aquatic therapy outcomes. Further research could explore combined aquatic and land-based rehabilitation, and the use of three-arm designs, including a non-exercise control to disentangle medium-specific from general exercise effects.
5. Conclusions
This systematic review suggests that hydrotherapy improves functional performance, gait-related parameters, and patient-reported outcomes in individuals with KOA. Positive effects were most consistently observed for walking capacity, sit-to-stand performance, pain and self-reported physical function. However, the certainty of evidence remains low to moderate, as determined by the GRADE assessments, due to heterogeneity in intervention protocols and outcome measures, small sample sizes, and the limited number of trials assessing functional performance and gait-related methods and outcome measures. While hydrotherapy has demonstrated effects comparable to land-based exercise in several studies, current evidence does not consistently support its superiority. Nevertheless, it appears to represent a feasible and clinically relevant rehabilitation option for patients with KOA. Further high-quality studies using standardized gait analysis protocols are needed to clarify the long-term effects of hydrotherapy on gait biomechanics and functional rehabilitation for KOA patients.
Supplementary Materials
The following supporting information can be downloaded at https://www.mdpi.com/article/10.3390/medicina62050994/s1: Table S1: PRISMA checklist, Table S2: Functional performance tests description.
Author Contributions
Conceptualization, M.M. and M.-G.I.; methodology, M.M. and M.-G.I.; software, M.M. and A.-D.N.; validation, M.-G.I., V.-M.C. and L.I.; formal analysis, A.-D.N.; investigation, M.M., A.-A.L. and A.-D.N.; resources, M.M.; data curation, M.M. and M.-G.I.; writing—original draft preparation, M.M., A.-A.L.; writing—review and editing, M.M., A.-A.L., A.-D.N. and M.-G.I.; visualization, M.M., V.-M.C. and L.I.; supervision, M.-G.I.; project administration, M.-G.I. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in this study are included in the article/Supplementary Materials. Further inquiries can be directed to the corresponding authors.
Acknowledgments
This study was conducted in the Research Nucleus of Balneal and Rehabilitation Sanatorium of Techirghiol, Romania.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| # | Cannot be calculated or extracted |
| & | And |
| ↑ | Statistically significant improvement |
| ↓ | Statistically significant decrease |
| °C | Degrees Celsius |
| 1RM | One-repetition maximum |
| 10MWT | 10-meter walk test |
| 5STS | The five times sit-to-stand |
| 6MWT | Six-minute walking test |
| ACR | American College of Rheumatology |
| AT | Anaerobic threshold |
| BMI | Body mass index |
| CG | CG |
| cm | Centimeter |
| DCCR | Direct co-contraction rate |
| DXA | Dual-energy X-ray absorptiometry |
| EMG | Electromyography |
| FPW-40 | 40 m fast-paced walk test |
| FU | Follow-up |
| GRADE | Grading of recommendations assessment, development and evaluation |
| GRF | Ground reaction forces |
| HAQ-DI | Health assessment questionnaire disability index |
| HR | Heart rate |
| IG | Interventional group |
| IGs | Intervention groups |
| KAM | Knee adduction moment |
| K-L | Kellgren–Laurence radiological stage |
| KOA | Knee osteoarthritis |
| KOOS | Knee injury and OA outcome score |
| LKE | Left knee extension |
| LKF | Left knee flexion |
| LTPA | Leisure-time physical activity |
| m | Meters |
| m/s | Meters/seconds |
| MeSH | Medical subject headings |
| min | Minute |
| NET | Total muscle activation |
| No | Number |
| No P | Total number of participants |
| NR | Not reported |
| NRS | Numeric rating scale |
| ns | No significant |
| OARSI | Osteoarthritis Research Society International |
| PICO | Population, intervention, comparator, and outcome |
| Post-E HR | Post-exercise heart rate |
| PRISMA | Preferred reporting items for systematic reviews and meta-analyses |
| PROSPERO | International Prospective Register of Systematic Reviews |
| QS | Quadriceps stretching |
| QoL | Quality of life |
| RCT | Randomized controlled trial |
| RF | Rectus femoris |
| RMS | Average muscle activity |
| RKF | Right knee flexion |
| RoB2 | Risk of bias tool for randomized trials |
| ROM | Range of motion |
| s | Second |
| SCT | The stair climb test |
| SCT-30 | 30 s chair stand test |
| SD | Standard deviation |
| SF-36 | Short Form-36 |
| SM | Semimembranosus |
| ST | Stair test |
| TUG Test | Timed Up and Go test |
| UKK 2 km | UKK Institute for Health Promotion Research 2km test |
| VAS | Visual Analogue Scale |
| VO2max | Maximum oxygen consumption |
| vs. | Versus |
| WHOQOL-100 | Self-quality assessment scale developed by the World Health Organization |
| WOMAC | Western Ontario and McMaster University’s Osteoarthritis Index |
References
- Ren, J.L.; Yang, J.; Hu, W. The global burden of osteoarthritis knee: A secondary data analysis of a population-based study. Clin. Rheumatol. 2025, 44, 1769–1810. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Kamal, K.C.; Kamal, A.M.; Kamal, D.; Fugaru, O.; Matei, D.; Trăistaru, M.R. Gait Analysis as a Measure of Physical Performance in Older Adults with Bilateral Knee Osteoarthritis. Medicina 2025, 61, 2118. [Google Scholar] [CrossRef] [Scilit] [PubMed] [PubMed Central]
- Bannuru, R.R.; Osani, M.C.; Vaysbrot, E.E.; Arden, N.K.; Bennell, K.; Bierma-Zeinstra, S.M.A.; Kraus, V.B.; Lohmander, L.S.; Abbott, J.H.; Bhandari, M.; et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthr. Cartil. 2019, 27, 1578–1589. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dias, J.M.; Cisneros, L.; Dias, R.; Fritsch, C.; Gomes, W.; Pereira, L.; Santos, M.L.; Ferreira, P.H. Hydrotherapy improves pain and function in older women with knee osteoarthritis: A randomized controlled trial. Braz. J. Phys. Ther. 2017, 21, 449–456. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Purser, J.L.; Golightly, Y.M.; Feng, Q.; Helmick, C.G.; Renner, J.B.; Jordan, J.M. Association of slower walking speed with incident knee osteoarthritis-related outcomes. Arthritis Care Res. 2012, 64, 1028–1035. [Google Scholar] [CrossRef] [Scilit]
- Dong, R.; Wu, Y.; Xu, S.; Zhang, L.; Ying, J.; Jin, H.; Wang, P.; Xiao, L.; Tong, P. Is aquatic exercise more effective than land-based exercise for knee osteoarthritis? Medicine 2018, 97, e13823. [Google Scholar] [CrossRef] [Scilit]
- Ma, J.; Chen, X.; Xin, J.; Niu, X.; Liu, Z.; Zhao, Q. Overall treatment effects of aquatic physical therapy in knee osteoarthritis: A systematic review and meta-analysis. J. Orthop. Surg. Res. 2022, 17, 190. [Google Scholar] [CrossRef] [Scilit]
- Noor, K.; Ahsan, M.A.; Bibi, S.; Mumtaz, T. The Effectiveness of Aquatic Exercises in Improving Balance and Gait in Patients with Knee Osteoarthritis: A Systematic Review. Pak. J. Med. Health Sci. 2023, 17, 416–422. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Booth, A.; Clarke, M.; Dooley, G.; Ghersi, D.; Moher, D.; Petticrew, M.; Stewart, L. The nuts and bolts of PROSPERO: An international prospective register of systematic reviews. Syst. Rev. 2012, 1, 2. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Enright, P.L. The six-minute walk test. Respir. Care 2003, 48, 783–785. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mylvaganam, S.; Nicolson, P.; Stanaitis, I.; Hawker, G.; King, L.K. Determinants of six-minute walk test performance in individuals with knee osteoarthritis. Osteoarthr. Cartil. Open 2026, 8, 100732. [Google Scholar] [CrossRef] [Scilit]
- Ng, S.S.M.; Ng, P.C.M.; Lee, C.Y.W.; Ng, E.S.; Tong, M.H.; Fong, S.S.; Tsang, W.W. Assessing the walking speed of older adults: The influence of walkway length. Am. J. Phys. Med. Rehabil. 2013, 92, 776–780. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oja, P.; Mänttäri, A.; Pokki, T.; Kukkonen-Harjula, K.; Laukkanen, R.; Malmberg, J.; Miilunpalo, S.; Suni, J. UKK Walk Test Tester’s Guide; UKK Institute for Health Promotion Research: Tampere, Finland, 2013. [Google Scholar]
- Podsiadlo, D.; Richardson, S. The Timed “Up & Go”: A Test of Basic Functional Mobility for Frail Elderly Persons. J. Am. Geriatr. Soc. 1991, 39, 142–148. [Google Scholar] [CrossRef] [Scilit]
- de Abreu, D.C.C.; Porto, J.M.; Tofani, P.S.; Braghin, R.M.B.; Freire Junior, R.C. Prediction of Reduced Gait Speed Using 5-Time Sit-to-Stand Test in Healthy Older Adults. J. Am. Med. Dir. Assoc. 2022, 23, 889–892. [Google Scholar] [CrossRef] [Scilit]
- Teo, T.; Mong, Y.; Ng, S. The repetitive Five-Times-Sit-To-Stand test: Its reliability in older adults. Int. J. Ther. Rehabil. 2013, 20, 122–130. [Google Scholar] [CrossRef] [Scilit]
- Dobson, F.; Hinman, R.S.; Roos, E.M.; Abbottm, J.H.; Stratford, P.; Davis, A.M.; Buchbinder, R.; Snyder-Mackler, L.; Henrotin, Y.; Thumboo, J.; et al. OARSI recommended performance-based tests to assess physical function in people diagnosed with hip or knee osteoarthritis. Osteoarthr. Cartil. 2013, 21, 1042–1052. [Google Scholar] [CrossRef] [Scilit]
- Nur, H.; Sertkaya, B.S.; Tuncer, T. Determinants of physical functioning in women with knee osteoarthritis. Aging Clin. Exp. Res. 2018, 30, 299–306. [Google Scholar] [CrossRef] [Scilit]
- Huskisson, E.C. Measurement of pain. Lancet 1974, 2, 1127–1131. [Google Scholar] [CrossRef] [Scilit]
- Hawker, G.A.; Mian, S.; Kendzerska, T.; French, M. Measures of adult pain: Visual Analog Scale for Pain (VAS Pain), Numeric Rating Scale for Pain (NRS Pain), McGill Pain Questionnaire (MPQ), Short-Form McGill Pain Questionnaire (SF-MPQ), Chronic Pain Grade Scale (CPGS), Short Form-36 Bodily Pain Scale (SF-36 BPS), and Measure of Intermittent and Constant Osteoarthritis Pain (ICOAP). Arthritis Care Res. 2011, 63, S240–S252. [Google Scholar]
- Bellamy, N.; Buchanan, W.W.; Goldsmith, C.H.; Campbell, J.; Stitt, L.W. Validation study of WOMAC: A health status instrument for measuring clinically important patient relevant outcomes to antirheumatic drug therapy in patients with osteoarthritis of the hip or knee. J. Rheumatol. 1988, 15, 1833–1840. [Google Scholar]
- Roos, E.M.; Roos, H.P.; Lohmander, L.S.; Ekdahl, C.; Beynnon, B.D. Knee Injury and Osteoarthritis Outcome Score (KOOS)—Development of a self-administered outcome measure. J. Orthop. Sports Phys. Ther. 1998, 28, 88–96. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ware, J.E.; Sherbourne, C.D. The MOS 36-item short-form health survey (SF-36). I. Conceptual framework and item selection. Med. Care 1992, 30, 473–483. [Google Scholar] [CrossRef] [Scilit]
- EuroQol Group. EuroQol—A new facility for the measurement of health-related quality of life. Health Policy 1990, 16, 199–208. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bruce, B.; Fries, J.F. The Health Assessment Questionnaire (HAQ). Clin. Exp. Rheumatol. 2005, 23, S14–S18. [Google Scholar] [PubMed]
- Zotero|Your Personal Research Assistant. Available online: https://www.zotero.org/ (accessed on 14 June 2025).
- Altman, R.; Asch, E.; Bloch, D.; Bole, G.; Borenstein, D.; Brandt, K.; Christy, W.; Cooke, T.D.; Greenwald, R.; Hochberg, M.; et al. Development of criteria for the classification and reporting of osteoarthritis. Classification of osteoarthritis of the knee. Arthritis Rheum. 1986, 29, 1039–1049. [Google Scholar] [CrossRef] [Scilit]
- Kellgren, J.H.; Lawrence, J.S. Radiological assessment of osteo-arthrosis. Ann. Rheum. Dis. 1957, 16, 494–502. [Google Scholar] [CrossRef] [Scilit]
- Risk of Bias|Cochrane. Available online: https://www.cochrane.org/learn/courses-and-resources/cochrane-methodology/risk-bias (accessed on 13 February 2026).
- Guyatt, G.; Oxman, A.D.; Akl, E.A.; Kunz, R.; Vist, G.; Brozek, J.; Norris, S.; Falck-Ytter, Y.; Glasziou, P.; DeBeer, H.; et al. GRADE guidelines: 1. Introduction-GRADE evidence profiles and summary of findings tables. J. Clin. Epidemiol. 2011, 64, 383–394. [Google Scholar] [CrossRef] [Scilit]
- Casilda-López, J.; Valenza, M.C.; Cabrera-Martos, I.; Díaz-Pelegrina, A.; Moreno-Ramírez, M.P.; Valenza-Demet, G. Effects of a dance-based aquatic exercise program in obese postmenopausal women with knee osteoarthritis: A randomized controlled trial. Menopause 2017, 24, 768–773. [Google Scholar] [CrossRef] [Scilit]
- Waller, B.; Munukka, M.; Rantalainen, T.; Lammentausta, E.; Nieminen, M.T.; Kiviranta, I.; Kautiainen, H.; Häkkinen, A.; Kujala, U.M.; Heinonen, A. Effects of high intensity resistance aquatic training on body composition and walking speed in women with mild knee osteoarthritis: A 4-month RCT with 12-month follow-up. Osteoarthr. Cartil. 2017, 25, 1238–1246. [Google Scholar] [CrossRef] [Scilit]
- Taglietti, M.; Facci, L.M.; Trelha, C.S.; de Melo, F.C.; da Silva, D.W.; Sawczuk, G.; Ruivo, T.M.; de Souza, T.B.; Sforza, C.; Cardoso, J.R. Effectiveness of aquatic exercises compared to patient-education on health status in individuals with knee osteoarthritis: A randomized controlled trial. Clin. Rehabil. 2018, 32, 766–776. [Google Scholar] [CrossRef] [Scilit]
- Kuptniratsaikul, V.; Kittichaikarn, C.; Suntornpiyapan, P.; Kovintaset, K.; Inthibal, S. Is four-week underwater treadmill exercise regimen compared to home exercise efficacious for pain relief and functional improvement in obese patients with knee osteoarthritis? A randomized controlled trial. Clin. Rehabil. 2019, 33, 85–93. [Google Scholar] [CrossRef] [Scilit]
- Arrieiro, A.N.; Mendonça, V.A.; Fonseca, S.F.; Santos, J.M.; Ribeiro, V.G.C.; Amorim, M.R.; Leopoldino, A.A.O.; Lacerda, A.C.R. Land-based versus water-based walking programs in elderly women with knee osteoarthritis: Preliminary results of a randomized clinical trial. Braz. J. Health Biomed. Sci. 2019, 18, 114–124. [Google Scholar] [CrossRef] [Scilit]
- Azizi, S.; Dadarkhah, A.; Rezasoltani, Z.; Raeissadat, S.A.; Mofrad, R.K.; Najafi, S. Randomized controlled trial of aquatic exercise for treatment of knee osteoarthritis in elderly people. Interv. Med. Appl. Sci. 2020, 11, 161–167. [Google Scholar] [CrossRef] [Scilit]
- Varzaityte, L.; Kubilius, R.; Rapoliene, L.; Bartuseviciute, R.; Balcius, A.; Ramanauskas, K.; Nedzelskiene, I. The effect of balneotherapy and peloid therapy on changes in the functional state of patients with knee joint osteoarthritis: A randomized, controlled, single-blind pilot study. Int. J. Biometeorol. 2020, 64, 955–964. [Google Scholar] [CrossRef] [Scilit]
- Garbi, F.P.; Rocha Júnior, P.R.; de Souza Pontes, N.; de Oliveira, A.; de Oliveira Barduzzi, G.; Villas Bôas, P.J.F. Aquatic physiotherapy in the functional capacity of elderly with knee osteoarthritis. Fisioter. Em Mov. 2021, 34, e34119. [Google Scholar] [CrossRef] [Scilit]
- Khruakhorn, S.; Chiwarakranon, S. Effects of hydrotherapy and land-based exercise on mobility and quality of life in patients with knee osteoarthritis: A randomized control trial. J. Phys. Ther. Sci. 2021, 33, 375–383. [Google Scholar] [CrossRef] [Scilit]
- Etesami, A.S.; Zolaktaf, V.; Esmaeili, H. Comparison of the Effect of 8 Weeks of Land Exercise Therapy and Hydrotherapy on Functional Activities of Elderly Women with Knee Osteoarthritis. Iran. J. Ageing 2022, 17, 154–169. [Google Scholar] [CrossRef] [Scilit]
- Jain, P.; Shinde, S. Effect of aquatic resistance, balance, and proprioception training on lower limb muscle performance in bilateral knee osteoarthritis. J. Musculoskelet. Surg. Res. 2025, 9, 104–111. [Google Scholar] [CrossRef] [Scilit]
- Kalkhoran, Z.B.; Khanmohammadi, R. Effects of Eight Weeks of Aquatic Therapy on Knee Proprioception and Gait Speed Among Female Older Adults with Knee Osteoarthritis: A Randomized Clinical Trial. Middle East J. Rehabil. Health Stud. 2024, 12, e157053. [Google Scholar]
- Pezeshk, A.F.; Zareie, F.; Ilbeigi, S. Hydrotherapy and Land-Based Exercise: Differential Impacts on Pain, Knee Biomechanics and Quadriceps Activation in Osteoarthritis. J. Sci. Sport Exerc. 2025. Epub ahead of print. [Google Scholar] [CrossRef] [Scilit]
- Vincent, H.K.; Heywood, K.; Connelley, J.; Hurley, R.W. Weight Loss and Obesity in the Treatment and Prevention of Osteoarthritis. PM&R 2012, 4, S59–S67. [Google Scholar]
- Ciurba (Pastor), A.-P.; Haidu, I.; Sîrbu, E.; Gavril, G.A.; Marcu, F.; Motofelea, A.C.; Boca, I.-C.; Ianc, D. The Impact of Mineral Water Balneotherapy on Pain and Physical Function in Patients with Knee Osteoarthritis: A Pilot Study. Balneo PRM Res. J. 2023, 14, 597. [Google Scholar] [CrossRef] [Scilit]
- Waller, B. The Effect of Aquatic Exercise on Symptoms, Function, Body Composition and Cartilage in Knee Osteoarthritis. Ph.D. Thesis, University of Jyväskylä, Jyväskylä, Finland, 2016. [Google Scholar]
- Lei, C.; Chen, H.; Zheng, S.; Pan, Q.; Xu, J.; Li, Y.; Liu, Y. The efficacy and safety of hydrotherapy in patients with knee osteoarthritis: A meta-analysis of randomized controlled trials. Int. J. Surg. 2024, 110, 1711–1722. [Google Scholar] [CrossRef] [Scilit]
- Xu, Z.; Wang, Y.; Zhang, Y.; Lu, Y.; Wen, Y. Efficacy and safety of aquatic exercise in knee osteoarthritis: A systematic review and meta-analysis of randomized controlled trials. Clin. Rehabil. 2023, 37, 330–347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Valenzuela, J.; Barahona-Vásquez, M.; López-Chaparro, M.; Martínez-Hernández, D.; Ávila, R.; Orellana, M.; Nova-Baeza, P.; Bruna, A.; Probst, V.S.; Sepúlveda-Loyola, W.A.; et al. Effectiveness of aquatic exercise versus other therapeutic modalities in patients with knee osteoarthritis pain: A systematic review with meta-analysis. Res. Sq. 2024. Epub ahead of print. [Google Scholar] [CrossRef] [Scilit]
- Richards, C.; Higginson, J.S. Knee contact force in subjects with symmetrical OA grades: Differences between OA severities. J. Biomech. 2010, 43, 2595–2600. [Google Scholar] [CrossRef] [Scilit]
- Zhang, L.; Ma, R.; Li, H.; Wan, X.; Xu, P.; Zhu, A.; Wei, P. Comparison of knee biomechanical characteristics during gait between patients with knee osteoarthritis and healthy individuals. Heliyon 2024, 10, e36931. [Google Scholar] [CrossRef] [Scilit]
- Lee, S.-H.; Kao, C.-C.; Liang, H.-W.; Wu, H.-T. Validity of the Osteoarthritis Research Society International (OARSI) recommended performance-based tests of physical function in individuals with symptomatic Kellgren and Lawrence grade 0-2 knee osteoarthritis. BMC Musculoskelet. Disord. 2022, 23, 1040. [Google Scholar] [CrossRef] [Scilit]
- Gianzina, E.; Yiannakopoulos, C.K.; Kalinterakis, G.; Delis, S.; Chronopoulos, E. Evaluation of the Timed Up and Go Test in Patients with Knee Osteoarthritis Using Inertial Sensors. Int. J. Transl. Med. 2025, 5, 2. [Google Scholar] [CrossRef] [Scilit]
- Wilson, R.; Chua, J.; Briggs, A.M.; Abbott, J.H. The cost-effectiveness of recommended adjunctive interventions for knee osteoarthritis: Results from a computer simulation model. Osteoarthr. Cartil. Open 2020, 2, 100123. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Published by MDPI on behalf of the Lithuanian University of Health Sciences. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.