


Abstract
Background and Objectives: Chronic pain is a significant global health issue, with conventional treatment strategies often proving insufficient or causing undesirable side effects. Interventional pain management techniques, including neuromodulation, have gained increasing interest as alternative therapeutic options. Cryoneurolysis, a technique leveraging extreme cold to modulate pain pathways, has emerged as a promising tool in chronic pain management. However, its efficacy and role within current clinical practice remain under evaluation. Methods: A narrative review was conducted by searching PubMed, Scopus, Embase, and Web of Science databases for studies published between 2010 and 2024 using the keywords “Cryoneurolysis”, “Cryoanalgesia”, “Cryoablation”, and “Chronic pain.” Only English-language studies were included. Studies that examined intraoperative cryoablation or lacked statistical analyses (except case reports) were excluded. Results: A total of 55 studies were included: 4 randomized controlled trials (RCTs), 16 retrospective studies, 4 prospective observational studies, and 31 case reports or small case series. The studies displayed significant heterogeneity in patient selection, targeted nerves, procedural protocols, and follow-up durations. While two RCTs demonstrated a significant pain reduction compared to control groups, other RCTs reported no significant improvement. Observational studies and case reports frequently report positive outcomes, with some achieving complete pain relief. Cryoneurolysis appears to be most effective in treating neuropathic pain, particularly in patients with peripheral nerve involvement. Conclusions: Cryoneurolysis is a safe technique for chronic pain management, which has been successfully applied, particularly for selected neuropathic pain conditions. However, the current evidence is limited by study heterogeneity and a lack of high-quality comparative trials. Further well-designed randomized studies are necessary to define its long-term efficacy and its potential role relative to other interventional pain therapies, such as radiofrequency ablation.
1. Introduction
Chronic pain is a global health concern that affects millions of people and imposes a significant burden on healthcare systems worldwide [1,2]. According to the International Association for the Study of Pain (IASP), it is defined as pain that persists or recurs for more than three months, often leading to a host of psychosocial, functional, and economic challenges [1,3]. Despite advancements in conventional medical management—including pharmacological interventions, physical therapy, and psychological support—many patients continue to experience intractable pain or are hindered by the side effects of long-term medication use [4,5]. These limitations have spurred interest in interventional pain therapies and neuromodulation techniques, which target specific pathways within the nervous system to modulate nociceptive signal transmission. Within the broader field of neuromodulation, a variety of approaches have been investigated for their ability to provide safe and sustained pain relief while minimizing adverse effects. Spinal cord stimulation (SCS), peripheral nerve stimulation (PNS), dorsal root ganglion (DRG) stimulation, deep brain stimulation (DBS), and motor cortex stimulation (MCS) are among the better-known therapies; however, novel modalities continue to emerge [6]. One of the most intriguing recent advances is cryoneurolysis (or cryoanalgesia), which leverages the application of ultra-low temperatures, typically in the range of −70 °C, to create a reversible conduction block in targeted peripheral nerves [7,8,9]. Unlike more traditional neurolytic procedures that rely on heat or chemical agents, cryoneurolysis preserves crucial connective tissues (e.g., the perineurium and epineurium), thereby reducing the likelihood of permanent damage while still providing meaningful analgesic effects. Cryoneurolysis involves the use of a highly pressurized cooling gas (nitrous oxide or carbon dioxide) circulating through a sealed probe. As the gas expands, pressure drops, decreasing the temperature and creating an ice ball at the tip, due to the Joule-Thomson effect [10]. Several factors influence the degree of analgesia obtainable with cryoneurolysis, specifically:
- The distance between the probe and the target nerve;
- The cryoprobe diameter;
- The size of the resulting ice ball;
- The temperature of the immediately surrounding tissue (such as blood, which acts as a heat sink);
- The rate and duration of cold application. The latter two factors are highly dependent upon the gas flow rate and the number of ‘freeze cycles’ applied, usually with 2–3 min of freezing followed by 0.5–2 min of thawing [11].
Lowering the temperature to more extreme values creates irreversible tissue damage; this application is called cryoablation [11]. Cryoablation and cryoneurolysis are different interventions with different mechanisms of action. Cryoablation involves the application of liquid nitrogen (reaching temperatures of −140 °C) to obtain irreversible tissue damage; cryoneurolysis reaches higher temperatures (−70 °C), allowing nerves to regenerate. In our search, we found that authors often consider these two terms as synonyms, both indicating a reversible nerve conduction block obtained with the application of cold temperatures. To include more studies and obtain a more complete overview of this technique in pain management, we decided to include all studies mentioning cryoablation, cryoneurolysis, or cryoanalgesia. Clinical interest in cryoneurolysis has expanded considerably, fueled by its demonstrated efficacy in managing refractory pain conditions, as well as its favorable safety profile. Indeed, evidence suggests that cryoneurolysis can be applied to both sensory and mixed nerves for various chronic pain syndromes, providing meaningful relief without the risks associated with permanent nerve destruction or high-dose analgesics [7,8]. Additionally, advances in imaging guidance (e.g., ultrasound, fluoroscopy, and computed tomography) have improved the accuracy of nerve localization, further enhancing procedure success and reducing complications. This narrative review aims to explore the evolving role of neuromodulation therapies, with a particular focus on cryoneurolysis and its potential to revolutionize chronic pain treatment. By examining principles, mechanisms, and clinical outcomes of cryoneurolysis across various chronic pain conditions, we hope to shed light on emerging best practices and inform the development of safer, more effective, and personalized interventions for individuals living with persistent pain.
2. Materials and Methods
We conducted a systematic search of PubMed, Embase, Web of Science, and the Cochrane Library for studies published between 2010 and 2025 examining the effects of cryoanalgesia on chronic pain. The research was conducted independently by all the authors. Search terms included “Cryoneurolysis,” “Cryoanalgesia,” “Cryoablation,” and “Chronic pain”; Boolean operators (AND, OR) were used to combine terms. The last search was conducted on 31 March 2025. We searched clinicaltrial.gov and EUDRACT for trials in progress on humans. We included randomized controlled trials, cohort studies, and case reports that evaluated the effects of Cryoanalgesia on Chronic pain. Papers were excluded from the analysis if they met one of the following criteria:
- -
- Papers describing the application of cryoneurolysis during a surgical procedure (i.e., intraoperative application on the intercostal nerves for post-thoracotomy pain).
- -
- Papers which did not report a statistical analysis (apart from case reports) or simply described a study protocol.
- -
- Reviews and all studies not including novel data.
- -
- Papers written in a non-English language.
Papers were searched and screened according to PRISMA guidelines.
3. Results
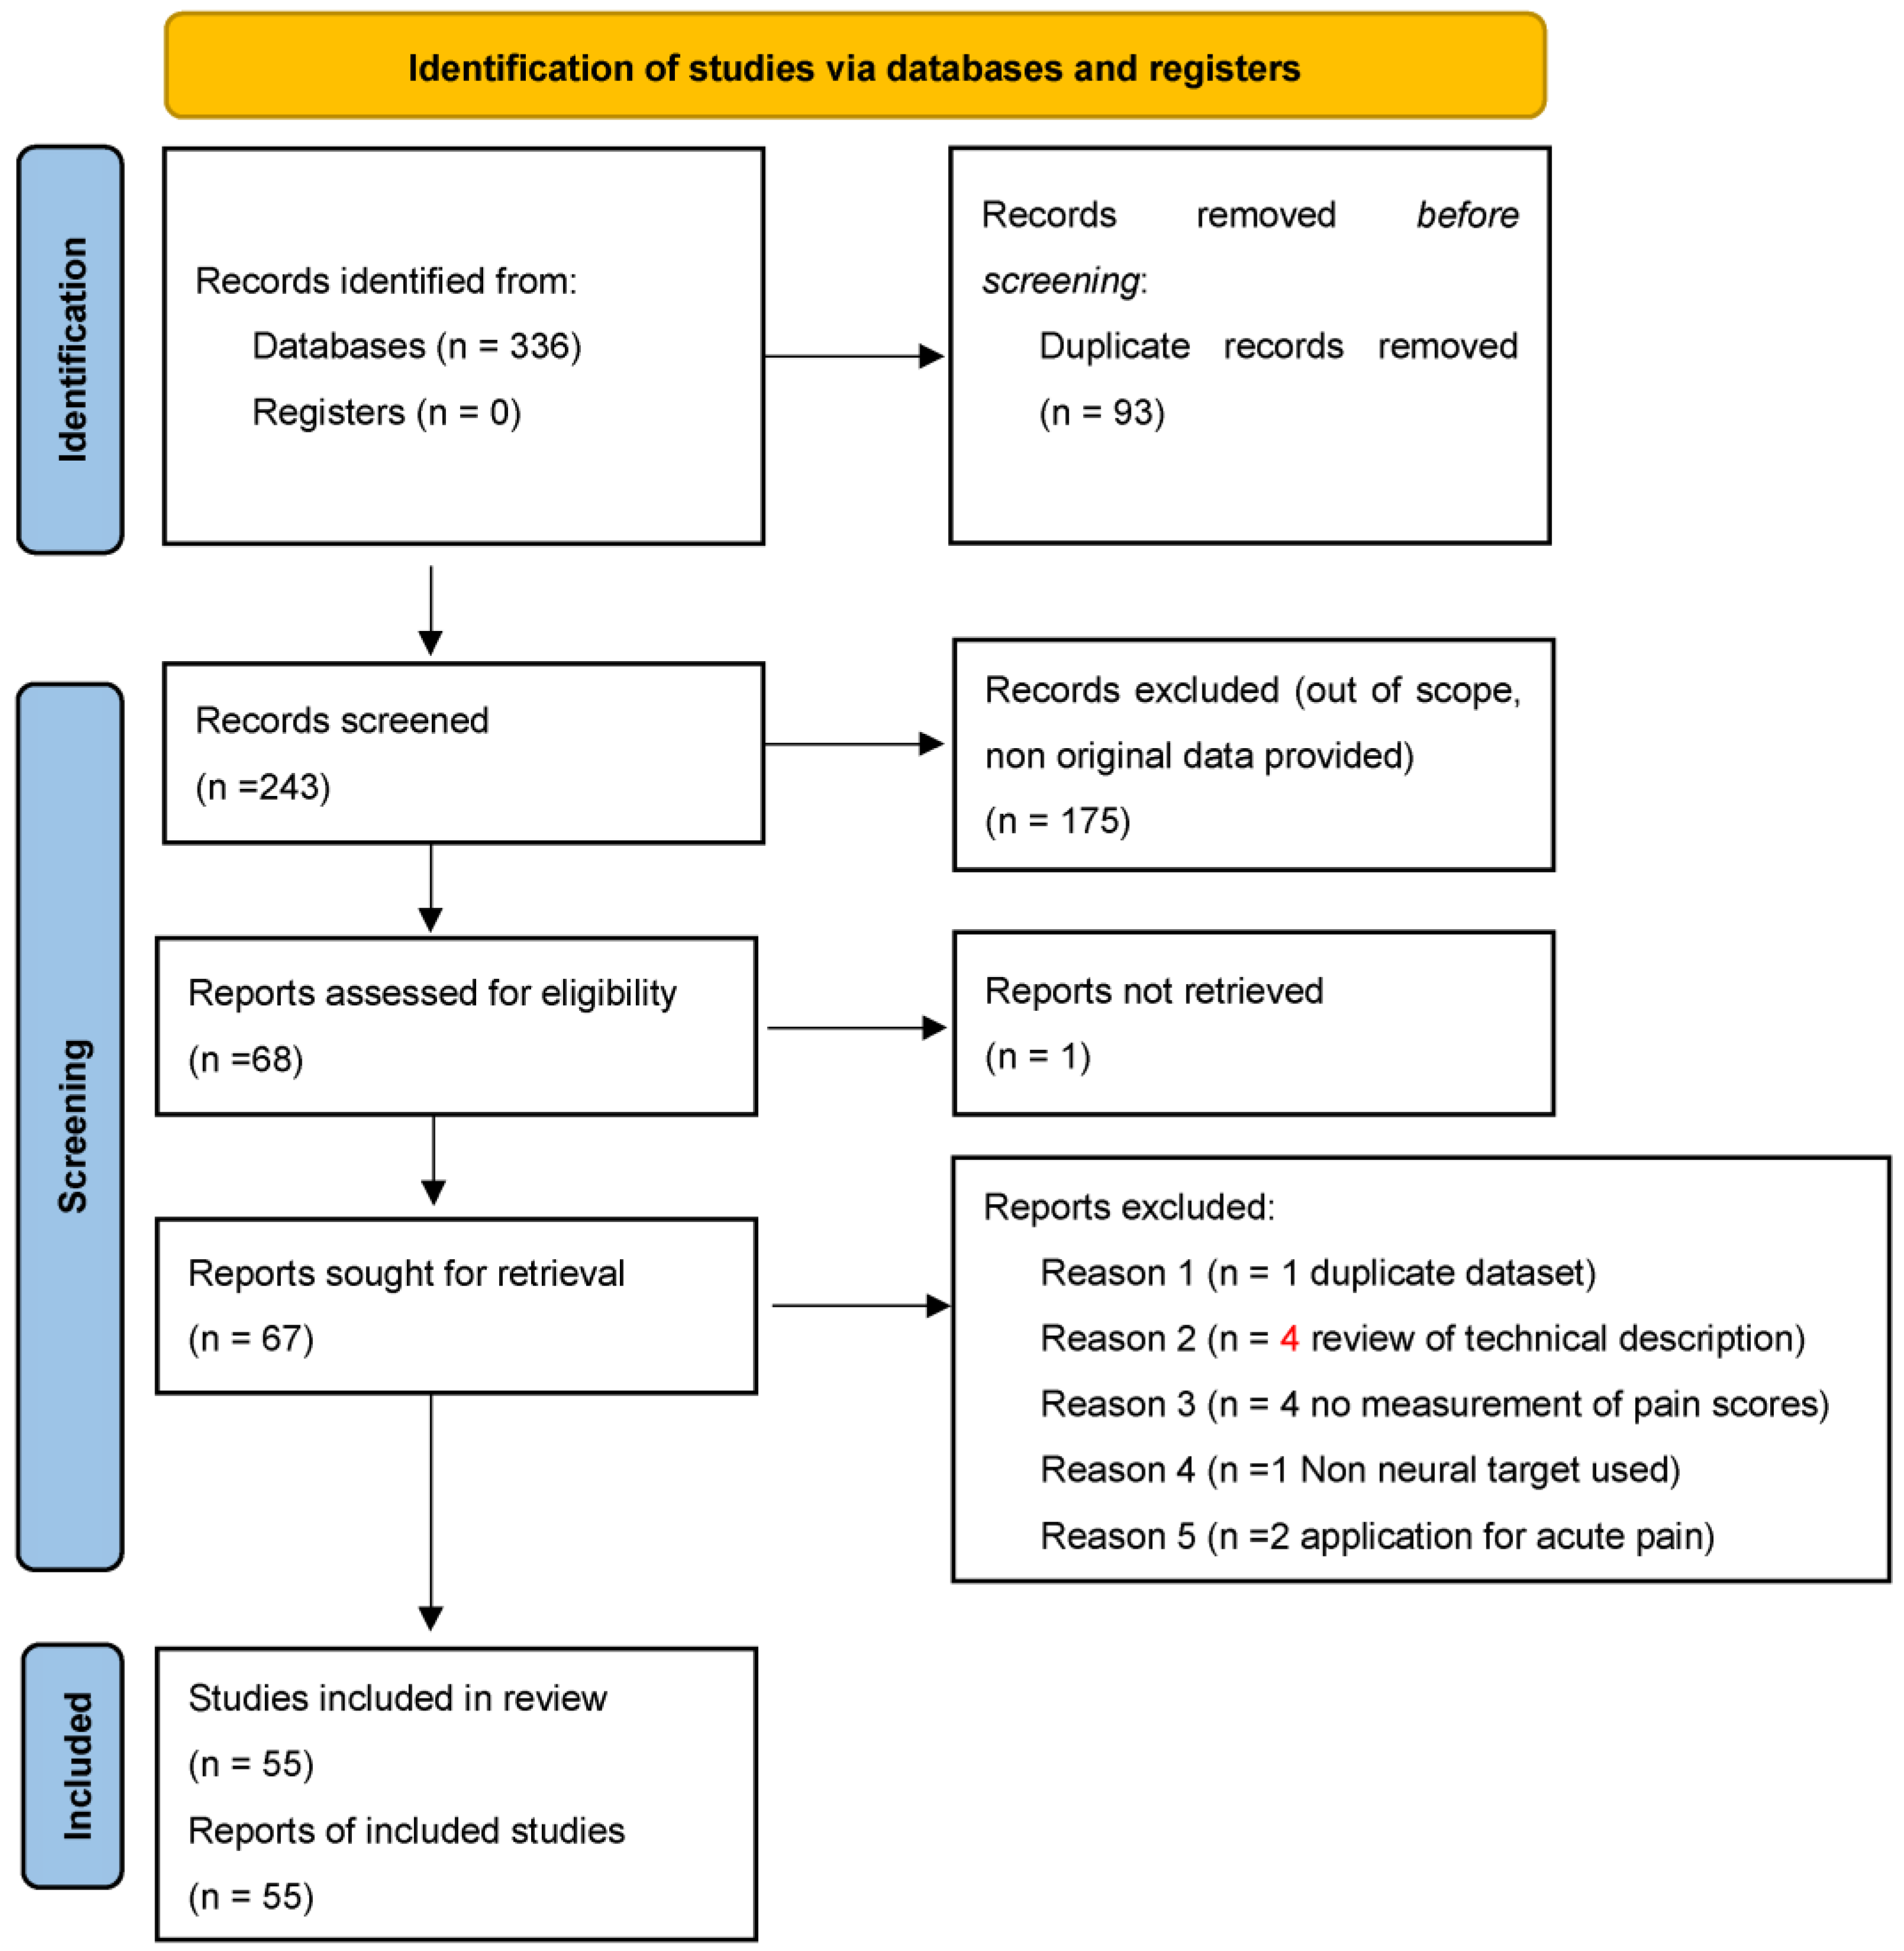
We present the number of identified articles, those screened, and those that fulfilled inclusion and exclusion criteria in the PRISMA flow chart.
Figure 1 reports the PRISMA Flow chart with included and excluded studies.
Figure 1.
Prisma flowchart.
After removing duplicates and excluding non-relevant papers, 55 studies were identified within our search parameters.
In total, 4 of these studies were RCTs, 16 were retrospective, 4 were prospective observational studies, and 31 were case reports or case series with less than 5 patients studied.
The included studies had very heterogeneous inclusion criteria (not all authors reported having performed a test block before cryoneurolysis, nociceptive and neuropathic pain were not differentiated, and different nerves were targeted).
Different devices were used with different protocols of treatment, but not all authors reported details of the temperature and number of cycles performed.
Targets were different as studies focused on different anatomical regions, and various nerves were treated.
Figure 2 represents anatomical regions investigated by different authors, intercostal nerves are the most studied targets, particularly for post thoracotomy chronic pain.
Figure 2.
Number of studies for each anatomical target.
The characteristics of the included studies are summarized in Table 1.
Table 1.
Characteristics of included studies.
In order to better define the effectiveness of cryoneurolysis, we narrowed our analysis on studies reporting a 6-month follow-up or longer and including a clear definition of meaningful pain relief (>50% from baseline). We stated the outcome as positive if more than 50% of patients reported more than 50% pain relief from baseline.
Table 2 shows the studies fulfilling these criteria.
Table 2.
Studies with a follow-up of 6 months or more and a definition of meaningful pain relief. Positive outcome is considered pain relief of more than 50% in more than 50% of patients.
4. Discussion
Despite the major interest in cryoneurolysis by pain physicians, the published evidence is modest.
Our analysis included four RCTs, with different anatomical targets, only two of which reported a positive outcome with a better response in the treatment group versus the comparison (sham or steroid injections).
Regarding retrospective and prospective studies, the results were overall stated as successful; however, most authors did not use a cutoff to define the success of the procedure, except for six studies who reported >50% pain relief at different follow up (generally less than six months), and one study with a success rate of 8% with a cutoff of only 30% pain relief [20,23,27,28,29,31,32].
Most authors reported only a mean decrease in NRS scores, ranging from 2 to 4.2 points of reduction.
All case reports and case series reported positive results, often with 100% pain relief.
Given the great heterogeneity of the included studies, it is not possible to draw a definite conclusion about the efficacy of cryoneurolysis; however, the published evidence indicates a favorable outcome for this technique, at least in the short term, with an excellent safety profile.
Narrowing the analysis on studies with a follow up of at least 6 months or more we found 16 studies, of which 9 were case reports or case series with less than 5 patients treated (Table 2).
No recommendations can be given regarding the best anatomical targets, since studies are very heterogeneous regarding targeted nerves. The best results were reported by the RCT of Radnovich et al. in 2017 [12]. The authors applied cryoneurolysis on the saphenous nerve, reporting a successful outcome at 4 months in more than 80% of patients. The saphenous nerve has been targeted (in its infrapatellar branch) by McLean, who reported more than 50% pain relief in all 23 patients treated, even if only 4 of them reached a 6-month follow-up [31].
A recent large study targeting the genicular nerves confirmed the positive outcomes associated with cryoneurolysis, even if the percentage of patients with >50% pain relief was reported only at a three-month follow-up [35].
Cryoneurolysis application on the occipital, sciatic, and medial branch nerves appears not to be supported by evidence since three RCTs reported no difference versus sham [13,14,15].
It is worth noticing that despite the poor evidence of efficacy for cryoneurolysis on chronic pain, several studies reported good outcomes for the application of the same technique for acute pain management, particularly for intercostal cryoablation to manage post thoracotomy acute pain.
Multiple reasons for this difference could be hypothesized, a more precise application on target nerves (given the direct visualization of nerves during thoracotomy or thoracoscopy), a more specific relation between the targeted nerves and the pain condition, a different pathophysiology of pain (marked central sensitization as in long lasting chronic pain could reduce the efficacy of peripherally focused neuromodulation techniques).
There are no reported comparisons of cryoablation with other interventional techniques, such as radiofrequency ablation, except for one RCT published in 2024. The authors did not report any improvement with cryoneurolysis compared to RF or placebo [13].
Even if this comparison is outside the scopes of this review, it must be observed that published evidence for radiofrequency ablation indicate generally more favorable outcomes for RF denervation in all the anatomical district where cryoneurolysis has been applied to [66,67,68].
For example, RF application for chronic knee, sacroiliac, or shoulder pain can provide sustained pain relief in more than 50% of patients up to 12 months; such results have not been observed with cryoneurolysis [66,67,68].
In our review, only three papers compared cryoneurolysis with RF application: one RCT (comparing cryo with Sham and RF) and two observational retrospective studies [13,29,45]. All of these studies reported better results with RF ablation than with cryoneurolysis.
Interesting results have been reported with the application of cryoneurolysis for neuropathic pain. Yoon et al. enrolled 22 patients for cryoneurolysis of refractory peripheral neuropathy on various nerves and showed significant mean reductions in VAS scores for pain over a 12-month period, maintaining a 50% pain relief at 6-month follow-up [18]. Another study reported the effects of cryoneurolysis on three patients with recalcitrant neuropathic anterior femoral cutaneous nerve pain [38]. Pain relief of more than 80% was maintained 1 year after the intervention. Lastly, a case report involving a refractory sural neuroma, with severe pain refractory to medications and repeated surgeries, reported significant and sustained pain relief after cryoablation [58]. The overall quality of the published evidence is very low, more than half of the included studies are case reports or case series, which are prone to publication bias (reporting only cases with positive outcome).
Most papers did not describe the protocol of cryoneurolysis used, since duration of application and temperature target are two critical factors in obtaining analgesia; this aspect is a serious limit to the quality of the evidence.
Regarding adverse events, cryoneurolysis can be considered a safe procedure. There are no reports of permanent nerve damage. The only contraindications are Raynaud syndrome, cryoglobulinemia, and cold urticaria [10]. The risks of cryoneurolysis are similar to other needle-based percutaneous procedures and include bleeding, bruising, and infection. Specific risks include permanent injury to the nerve, injury to the surrounding tissue, and discoloration of the skin if the cannula is retracted prior to resolving the ice ball and allowing contact with other areas near the target site [10].
Myonecrosis after cryoneurolysis for knee pain has been reported. It is not clear whether this complication was related to the procedure itself (the accidental transmission of nitrous oxide as a cooling gas into the tissue could increase the risk of infection) or to the transmission of skin bacteria into deep tissue during the procedure [69,70].
5. Conclusions
Cryoneurolysis is a safe technique, only few adverse events, mostly mild and self-limiting, have been reported. Its efficacy in chronic pain has been demonstrated only in the short-term (less than 6 months) follow-up for various targets (saphenous nerve, sciatic, intercostal, suprascapular).
Given the paucity and low quality of the studies, it is not possible to give recommendations for the application of cryoneurolysis for chronic pain and it cannot be considered a first line treatment.
More robust and well conducted studies are needed, to assess the intrinsic efficacy of cryoneurolysis and to compare it to existing technologies, such as radiofrequency ablation.
We suggest considering these aspects in future study designs:
- -
- Precise protocol description for cryoneurolysis application (temperature, duration of application, number of freezing cycles used);
- -
- Specific neural targets;
- -
- Specific patient population (i.e., chronic post-surgical pain after total joint replacement).
Author Contributions
Conceptualization, A.T. and G.L.B.; methodology, A.T., M.M. and G.L.B.; software A.T., M.M., S.M., C.S. and G.L.B., validation, A.T., M.M., S.M., C.S. and G.L.B.; formal analysis, A.T., M.M., S.M., C.S. and G.L.B.; investigation, A.T., M.M., S.M., C.S. and G.L.B.; data curation, A.T., M.M., S.M., C.S. and G.L.B.; writing—original draft preparation, A.T., M.M., S.M., C.S. and G.L.B.; writing—review and editing, A.T., M.M., S.M., C.S. and G.L.B.; visualization, A.T., M.M., S.M., C.S. and G.L.B.; supervision, A.T. and G.L.B. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Werner, M.U.; Kongsgaard, U.E. I. Defining Persistent Post-Surgical Pain: Is an Update Required? Br. J. Anaesth. 2014, 113, 1–4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cui, A.; Li, H.; Wang, D.; Zhong, J.; Chen, Y.; Lu, H. Global, Regional Prevalence, Incidence and Risk Factors of Knee Osteoarthritis in Population-Based Studies. EClinicalMedicine 2020, 29–30, 100587. [Google Scholar] [CrossRef] [Scilit]
- Baker, P.N.; Van Der Meulen, J.H.; Lewsey, J.; Gregg, P.J. The Role of Pain and Function in Determining Patient Satisfaction after Total Knee Replacement: Data from the National Joint Registry for England and Wales. J. Bone Joint Surg. Br. 2007, 89, 893–900. [Google Scholar] [CrossRef] [Scilit]
- Martel, M.O.; Finan, P.H.; Dolman, A.J.; Subramanian, S.; Edwards, R.R.; Wasan, A.D.; Jamison, R.N. Self-Reports of Medication Side Effects and Pain-Related Activity Interference in Patients with Chronic Pain: A Longitudinal Cohort Study. Pain 2015, 156, 1092–1100. [Google Scholar] [CrossRef] [Scilit]
- Poenaru, D.; Sandulescu, M.I.; Cinteza, D. Pain Modulation in Chronic Musculoskeletal Disorders: Botulinum Toxin, a Descriptive Analysis. Biomedicines 2023, 11, 1888. [Google Scholar] [CrossRef] [Scilit]
- Wylde, V.; Beswick, A.; Bruce, J.; Blom, A.; Howells, N.; Gooberman-Hill, R. Chronic Pain after Total Knee Arthroplasty. EFORT Open Rev. 2018, 3, 461–470. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Panagopoulos, A.; Tsiplakos, P.; Katsanos, K.; Antzoulas, P.; Lakoumentas, J. Cooled Radiofrequency Ablation versus Cryoneurolysis of the Genicular Nerves for the Symptomatic Pain Management in Knee Osteoarthritis: A Study Protocol of a Prospective, Randomized, Single-Blinded Clinical Trial. J. Orthop. Surg. 2023, 18, 295. [Google Scholar] [CrossRef] [Scilit]
- Slavin, B.R.; Markowitz, M.I.; Klifto, K.M.; Prologo, F.J.; Taghioff, S.M.; Dellon, A.L. Cryoanalgesia: Review with Respect to Peripheral Nerve. J. Reconstr. Microsurg. 2024, 40, 302–310. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wong, J.; Bremer, N.; Weyker, P.D.; Webb, C.A.J. Ultrasound-Guided Genicular Nerve Thermal Radiofrequency Ablation for Chronic Knee Pain. Case Rep. Anesthesiol. 2016, 2016, 8292450. [Google Scholar] [CrossRef] [Scilit]
- Ilfeld, B.M.; Finneran, J.J. Cryoneurolysis and Percutaneous Peripheral Nerve Stimulation to Treat Acute Pain: A Narrative Review. Anesthesiology 2020, 133, 1127–1149. [Google Scholar] [CrossRef] [Scilit]
- Ilfeld, B.M.; Gabriel, R.A.; Trescot, A.M. Ultrasound-Guided Percutaneous Cryoneurolysis for Treatment of Acute Pain: Could Cryoanalgesia Replace Continuous Peripheral Nerve Blocks? Br. J. Anaesth. 2017, 119, 709–712. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Radnovich, R.; Scott, D.; Patel, A.T.; Olson, R.; Dasa, V.; Segal, N.; Lane, N.E.; Shrock, K.; Naranjo, J.; Darr, K.; et al. Cryoneurolysis to Treat the Pain and Symptoms of Knee Osteoarthritis: A Multicenter, Randomized, Double-Blind, Sham-Controlled Trial. Osteoarthritis Cartilage 2017, 25, 1247–1256. [Google Scholar] [CrossRef] [Scilit]
- Truong, K.; Meier, K.; Ahrens, L.C.; Wichmann, T.O.; Zaer, H.; Tiroke, L.H.; Arvin, S.; Bazys, M.; Duel, P.; Gudmundsdottir, G.; et al. Cryoneurolysis versus Radiofrequency Ablation Outcome on Pain Experience in Chronic Low Back Pain (COPE): A Single-Blinded Randomised Controlled Trial. RMD Open 2024, 10, e004196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ilfeld, B.M.; Smith, C.R.; Turan, A.; Mariano, E.R.; Miller, M.E.; Fisher, R.L.; Trescot, A.M.; Cohen, S.P.; Eisenach, J.C.; Sessler, D.I.; et al. Ultrasound-Guided Percutaneous Cryoneurolysis to Treat Chronic Postamputation Phantom Limb Pain: A Multicenter Randomized Controlled Trial. Anesthesiology 2023, 138, 82–97. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kvarstein, G.; Högström, H.; Allen, S.M.; Rosland, J.H. Cryoneurolysis for Cervicogenic Headache—A Double Blinded Randomized Controlled Study. Scand. J. Pain 2019, 20, 39–50. [Google Scholar] [CrossRef] [Scilit]
- Grigsby, E.; Radnovich, R.; Nalamachu, S. Efficacy and Safety of Cryoneurolysis for Treatment of Chronic Head Pain Secondary to Occipital Neuralgia: A Pilot Study. Local Reg. Anesth. 2021, 14, 125–132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Perry, T.A.; Segal, N.A. An Open-Label, Single-Arm Trial of Cryoneurolysis for Improvements in Pain, Activities of Daily Living and Quality of Life in Patients with Symptomatic Ankle Osteoarthritis. Osteoarthr. Cartil. Open 2022, 4, 100272. [Google Scholar] [CrossRef] [Scilit]
- Yoon, J.H.E.; Grechushkin, V.; Chaudhry, A.; Bhattacharji, P.; Durkin, B.; Moore, W. Cryoneurolysis in Patients with Refractory Chronic Peripheral Neuropathic Pain. J. Vasc. Interv. Radiol. 2016, 27, 239–243. [Google Scholar] [CrossRef] [Scilit]
- Zhan, C.; Yoon, J.; Baghai Kermani, A.; Gupta, A.; Moore, W. Abstract No. 587 Safety and Efficacy of Computed Tomography–Guided Percutaneous Cryoneurolysis for Chronic Intercostal Pain Syndrome. J. Vasc. Interv. Radiol. 2020, 31, S256. [Google Scholar] [CrossRef] [Scilit]
- Das, G.; Das, S.; Sahoo, R.; Shreyas, S.; Kanthi, B.; Sharma, V.S. Efficacy of Cryoneurolysis versus Intra-Articular Steroid in Sacroiliac Joint Pain: A Retrospective, Case-Control Study. Indian J. Anaesth. 2023, 67, 1004–1008. [Google Scholar] [CrossRef] [Scilit]
- Sidebottom, A.J.; Carey, E.C.; Madahar, A.K. Cryoanalgesia in the Management of Intractable Pain in the Temporomandibular Joint: A Five-Year Retrospective Review. Br. J. Oral Maxillofac. Surg. 2011, 49, 653–656. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Prologo, J.D.; Gilliland, C.A.; Miller, M.; Harkey, P.; Knight, J.; Kies, D.; Hawkins, C.M.; Corn, D.; Monson, D.K.; Edalat, F.; et al. Percutaneous Image-Guided Cryoablation for the Treatment of Phantom Limb Pain in Amputees: A Pilot Study. J. Vasc. Interv. Radiol. 2017, 28, 24–34.e4. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yasin, J.; Thimmappa, N.; Kaifi, J.T.; Avella, D.M.; Davis, R.; Tewari, S.O.; Saboo, S.S.; Bhat, A. CT-Guided Cryoablation for Post-Thoracotomy Pain Syndrome: A Retrospective Analysis. Diagn. Interv. Radiol. 2020, 26, 53–57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moore, W.; Kolnick, D.; Tan, J.; Yu, H.S. CT Guided Percutaneous Cryoneurolysis for Post Thoracotomy Pain Syndrome. Acad. Radiol. 2010, 17, 603–606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wolter, T.; Deininger, M.; Hubbe, U.; Mohadjer, M.; Knoeller, S. Cryoneurolysis for Zygapophyseal Joint Pain: A Retrospective Analysis of 117 Interventions. Acta Neurochir. 2011, 153, 1011–1019. [Google Scholar] [CrossRef] [Scilit]
- Kim, C.H.; Hu, W.; Gao, J.; Dragan, K.; Whealton, T.; Julian, C. Cryoablation for the Treatment of Occipital Neuralgia. Pain Physician 2015, 18, E363–E368. [Google Scholar] [CrossRef] [Scilit]
- Nemecek, Z.; Sturm, C.; Rauen, A.C.; Reisig, F.; Streitberger, K.; Harnik, M.A. Ultrasound-Controlled Cryoneurolysis for Peripheral Mononeuropathies: A Retrospective Cohort Study. Pain Manag. 2023, 13, 363–372. [Google Scholar] [CrossRef] [Scilit]
- Parekattil, S.; Gudeloglu, A.; Ergun, O.; Galante, A.; Etafy, M.; Mendelson, R. MP31-10 A Cost Effective Office Based Technique for Ultrasound Guided Peri-Spermatic Cord Cryoablation for Chronic Scrotal Content Pain. J. Urol. 2021, 206, e558–e559. [Google Scholar] [CrossRef] [Scilit]
- Tinnirello, A. Genicular Nerves Ablation for Chronic Knee Pain: A Single-Center Retrospective Evaluation Comparing Four Ablation Modalities. Pain Pract. 2020, 20, 7–95. [Google Scholar] [CrossRef] [Scilit]
- Nezami, N.; Behi, A.; Manyapu, S.; Meisel, J.L.; Resnick, N.; Corn, D.; Prologo, J.D. Percutaneous CT-Guided Cryoneurolysis of the Intercostobrachial Nerve for Management of Postmastectomy Pain Syndrome. J. Vasc. Interv. Radiol. 2023, 34, 807–813. [Google Scholar] [CrossRef] [Scilit]
- McLean, B.C.; Nguyen, C.D.; Newman, D.P. Cryoablation of the Infrapatellar Branch of the Saphenous Nerve Identified by Non-Invasive Peripheral Nerve Stimulator for the Treatment of Non-Surgical Anterior Knee Pain: A Case Series and Review of the Literature. Cureus 2020, 12, e8747. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Calixte, N.; Kartal, I.G.; Tojuola, B.; Gudeloglu, A.; Etafy, M.; Brahmbhatt, J.V.; Mendelson, R.A.; Chetta, M.; Parekattil, S.J. Salvage Ultrasound-Guided Targeted Cryoablation of The Perispermatic Cord For Persistent Chronic Scrotal Content Pain After Microsurgical Denervation Of The Spermatic Cord. Urology 2019, 130, 181–185. [Google Scholar] [CrossRef] [Scilit]
- Bellini, M.; Barbieri, M. Percutaneous Cryoanalgesia in Pain Management: A Case-Series. Anestezjol. Intensywna Ter. 2015, 47, 131–133. [Google Scholar] [CrossRef] [Scilit]
- Prologo, J.; Mittal, A.; Knight, J.; Hsu, D.; Dolan, R.; Com, D. Percutaneous CT-Guided Cryoablation for the Management of Pudendal Neuralgia: Long-Term Outcomes. J. Vasc. Interv. Radiol. 2018, 29, S241–S242. [Google Scholar]
- Lo Bianco, G.; D’angelo, F.P.; Dos Santos, G.F.; Stogicza, A.; Leoni, M.L.G.; Trescot, A.M.; Yong, R.J.; Robinson, C.L. Genicular Nerve Ultrasound-Guided Cryoanalgesia for the Treatment of Chronic Knee Joint Pain: An Observational Retrospective Study. Pain Ther. 2025, 14, 985–998. [Google Scholar] [CrossRef] [Scilit]
- Filipovski, I.; Gabriel, R.A.; Kestenholz, R. Ultrasound-Guided Cryoneurolysis for the Treatment of Painful Diabetic Neuropathy of the Foot: A Case Series. Cureus 2024, 16, e56267. [Google Scholar] [CrossRef] [Scilit]
- Stogicza, A.R.; Peng, P. Cryoanalgesia for Shoulder Pain: A Motor-Sparing Approach to Rotator Cuff Disease. Reg. Anesth. Pain Med. 2022, 47, 576–580. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dalili, D.; Ahlawat, S.; Rashidi, A.; Belzberg, A.J.; Fritz, J. Cryoanalgesia of the Anterior Femoral Cutaneous Nerve (AFCN) for the Treatment of Neuropathy-Mediated Anterior Thigh Pain: Anatomy and Technical Description. Skeletal Radiol. 2021, 50, 1227–1236. [Google Scholar] [CrossRef] [Scilit]
- Moesker, A.A.; Karl, H.W.; Trescot, A.M. Treatment of Phantom Limb Pain by Cryoneurolysis of the Amputated Nerve. Pain Pract. 2014, 14, 52–56. [Google Scholar] [CrossRef] [Scilit]
- Sahoo, R.K.; Das, G.; Pathak, L.; Dutta, D.; Roy, C.; Bhatia, A. Cryoneurolysis of Innervation to Sacroiliac Joints: Technical Description and Initial Results—A Case Series. AA Pract. 2021, 15, e01427. [Google Scholar] [CrossRef] [Scilit]
- Mendes-Andrade, I.; Pagan-Rosado, R.; Ferreira-Silva, N.; Hurdle, M.F. A Novel Approach to Refractory Coccydynia: Ultrasound- Fluoroscopy-Guided Cryoablation of Sacrococcygeal Nerve. Pain Manag. 2024, 14, 541–547. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaffer, J.P.; Williams, V.B.; Shin, S.S. Cryoneurolysis for Digital Neuralgia in Professional Baseball Players: A Case Series. Orthop. J. Sports Med. 2022, 10, 23259671221096095. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gabriel, R.A.; Kestenholz, R.; Filipovski, I. Repeated Ultrasound-Guided Percutaneous Intercostal Cryoneurolysis for the Management of Chronic Postmastectomy Pain Syndrome: A Case Report. AA Pract. 2024, 18, e01764. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cachemaille, M.; Geering, S.; Broome, M. Cryoneurolysis of Alveolar Nerves for Chronic Dental Pain: A New Technique and a Case Series. Pain Pract. 2023, 23, 851–854. [Google Scholar] [CrossRef] [Scilit]
- Kočan, L.; Rapčan, R.; Sudzina, R.; Rapčanová, S.; Rybár, D.; Mláka, J.; Kočanová, H.; Buriánek, M.; Vašková, J. Radiofrequency Denervation and Cryoablation of the Lumbar Zygapophysial Joints in the Treatment of Positive Lumbar Facet Joint Syndrome—A Report of Three Cases. Radiol. Case Rep. 2022, 17, 4515–4520. [Google Scholar] [CrossRef] [Scilit]
- Connelly, N.R.; Malik, A.; Madabushi, L.; Gibson, C. Use of Ultrasound-Guided Cryotherapy for the Management of Chronic Pain States. J. Clin. Anesth. 2013, 25, 634–636. [Google Scholar] [CrossRef] [Scilit]
- Matelich, B.; Berg, A.; Habeck, J.; Hutchins, J. B32 Ultrasound-Guided Cryoneurolysis of the Supra Scapular Nerve for Chronic Shoulder Pain: A Case Series. Reg. Anesth. Pain Med. 2022, 47, A99. [Google Scholar]
- Fox, S. Pudendal Nerve Cryoablation for Chronic Pelvic Pain. Dis. Colon Rectum 2019, 62, e39–e401. [Google Scholar] [CrossRef] [Scilit]
- Sarridou, D.; Papadopoulou, D.; Paraskevopoulos, T.; Stavropoulou, E. Successful Treatment of Complex Regional Pain Syndrome Type 1 of Upper Limb with Cryoneurolysis of the Stellate Ganglion: A Rare Case Report. Pain Pract. 2022, 22, 285–287. [Google Scholar] [CrossRef] [Scilit]
- Ramsook, R.; Spinner, D. (468) Cryoablation of a Hip Disarticulation Residual Limb Neuroma Allowing for Ambulation and Pain Relief: A Case Report. J. Pain 2016, 17, S91. [Google Scholar] [CrossRef] [Scilit]
- Joshi, D.H.; Thawait, G.K.; Del Grande, F.; Fritz, J. MRI-Guided Cryoablation of the Posterior Femoral Cutaneous Nerve for the Treatment of Neuropathy-Mediated Sitting Pain. Skeletal Radiol. 2017, 46, 983–987. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kalava, A.; Pham, K.; Okon, S. Cryoneurolysis of the Subcostal Nerve: A Technical Description and Case Report. Cureus 2024, 16, e57521. [Google Scholar] [CrossRef] [Scilit]
- Sen, S.; De Haan, J.B.; Mehrafza, M.; Hernandez, N. Ultrasound-Guided Percutaneous Intercostal Cryoneurolysis for Acute-on-Chronic Pain in CLOVES Syndrome. Cureus 2023, 15, e34066. [Google Scholar] [CrossRef] [Scilit]
- Jung, E.Y.; Lee, S.S. Treatment of Chronic Mini-Thoracotomy Wound Pain and Lung Herniation with Intercostal Cryoablation and Surgical Mesh Repair: A Case Report. J. Cardiothorac. Surg. 2024, 19, 348. [Google Scholar] [CrossRef] [Scilit]
- MacRae, F.; Speirs, A.; Bursuc, A.; Hashemi, M.; Winston, P. A Case Report of Cryoneurolysis for Dorsal Foot Pain and Toe Clawing in a Patient With Multiple Sclerosis. Arch. Rehabil. Res. Clin. Transl. 2023, 5, 100286. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Perese, J.; Oswald, J.; Gabriel, R.A. Ultrasound-Guided Percutaneous Cryoneurolysis for Post-Thoracotomy Pain Syndrome: A Case Report. Cureus 2022, 14, e328. [Google Scholar] [CrossRef] [Scilit]
- Koethe, Y.; Mannes, A.J.; Wood, B.J. Image-Guided Nerve Cryoablation for Post-Thoracotomy Pain Syndrome. Cardiovasc. Intervent. Radiol. 2014, 37, 843–846. [Google Scholar] [CrossRef] [Scilit]
- Rhame, E.E.; DeBonet, A.F.; Simopoulos, T.T. Ultrasonographic Guidance and Characterization of Cryoanalgesic Lesions in Treating a Case of Refractory Sural Neuroma. Case Rep. Anesthesiol. 2011, 2011, 691478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- MacRae, F.; Boissonnault, E.; Hashemi, M.; Winston, P. Bilateral Suprascapular Nerve Cryoneurolysis for Pain Associated With Glenohumeral Osteoarthritis: A Case Report. Arch. Rehabil. Res. Clin. Transl. 2023, 5, 100256. [Google Scholar] [CrossRef] [Scilit]
- Weber, G.; Saad, K.; Awad, M.; Wong, T.H. Case Report Of Cryoneurolysis For The Treatment of Refractory Intercostobrachial Neuralgia With Postherpetic Neuralgia. Local Reg. Anesth. 2019, 12, 103–107. [Google Scholar] [CrossRef] [Scilit]
- Yarmohammadi, H.; Nakamoto, D.; Azar, N.; Hayek, S.; Haaga, J. Percutaneous Computed Tomography Guided Cryoablation of the Celiac Plexus as an Alternative Treatment for Intractable Pain Caused by Pancreatic Cancer. J. Cancer Res. Ther. 2011, 7, 481. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rupp, A.; Panchang, P.; Smith, M. A Case Report of Cryoablation for Chronic Shoulder Pain Due to Osteoarthritis. Interv. Pain Med. 2022, 1, 100146. [Google Scholar] [CrossRef] [Scilit]
- Kalava, A.; Kassie, R.; Borick, E. Cryoneurolysis of Intercostal Nerves for Postherpetic Neuralgia: A Case Report. Cureus 2024, 16, e70557. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hampton, H.; Kalava, A. Ischiorectal Approach to Cryoablation of the Pudendal Nerve Using a Handheld Device: A Report of Two Cases. Cureus 2023, 15, e44377. [Google Scholar] [CrossRef] [Scilit]
- Fiala, M.; Azariah, A.; Woo, J.; Aal, A.K.A.; Levey, A. Treating Phantom Limb Pain: Cryoablation of the Posterior Tibial Nerve. Radiol. Case Rep. 2022, 17, 3168–3171. [Google Scholar] [CrossRef] [Scilit]
- Davis, T.; Loudermilk, E.; DePalma, M.; Hunter, C.; Lindley, D.A.; Patel, N.; Choi, D.; Soloman, M.; Gupta, A.; Desai, M.; et al. Twelve-Month Analgesia and Rescue, by Cooled Radiofrequency Ablation Treatment of Osteoarthritic Knee Pain: Results from a Prospective, Multicenter, Randomized, Cross-over Trial. Reg. Anesth. Pain Med. 2019, 44, 499–506. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Santi, C.; Haag, T.; Cooke, C.; Schatman, M.; Tinnirello, A. Two-Centre Retrospective Analysis on Selective Sensory Denervation of Shoulder Joint by Means of Cooled Radiofrequency in Chronic Shoulder Pain. J. Pain Res. 2024, 17, 3139–3150. [Google Scholar] [CrossRef] [Scilit]
- Klessinger, S.; Casser, H.-R.; Gillner, S.; Koepp, H.; Kopf, A.; Legat, M.; Meiler, K.; Norda, H.; Schneider, M.; Scholz, M.; et al. Radiofrequency Denervation of the Spine and the Sacroiliac Joint: A Systematic Review Based on the Grades of Recommendations, Assesment, Development, and Evaluation Approach Resulting in a German National Guideline. Glob. Spine J. 2024, 14, 2124–2154. [Google Scholar] [CrossRef] [Scilit]
- Cahani, D.; Chacko, J.; Hahn, B. Myonecrosis: A Rare Complication of Cryoneurolysis. J. Emerg. Med. 2019, 57, e73–e76. [Google Scholar] [CrossRef] [Scilit]
- Fleischmann, E.; Lenhardt, R.; Kurz, A.; Herbst, F.; Fülesdi, B.; Greif, R.; Sessler, D.I.; Akça, O. Nitrous Oxide and Risk of Surgical Wound Infection: A Randomised Trial. Lancet 2005, 366, 1101–1107. [Google Scholar] [CrossRef] [Scilit]
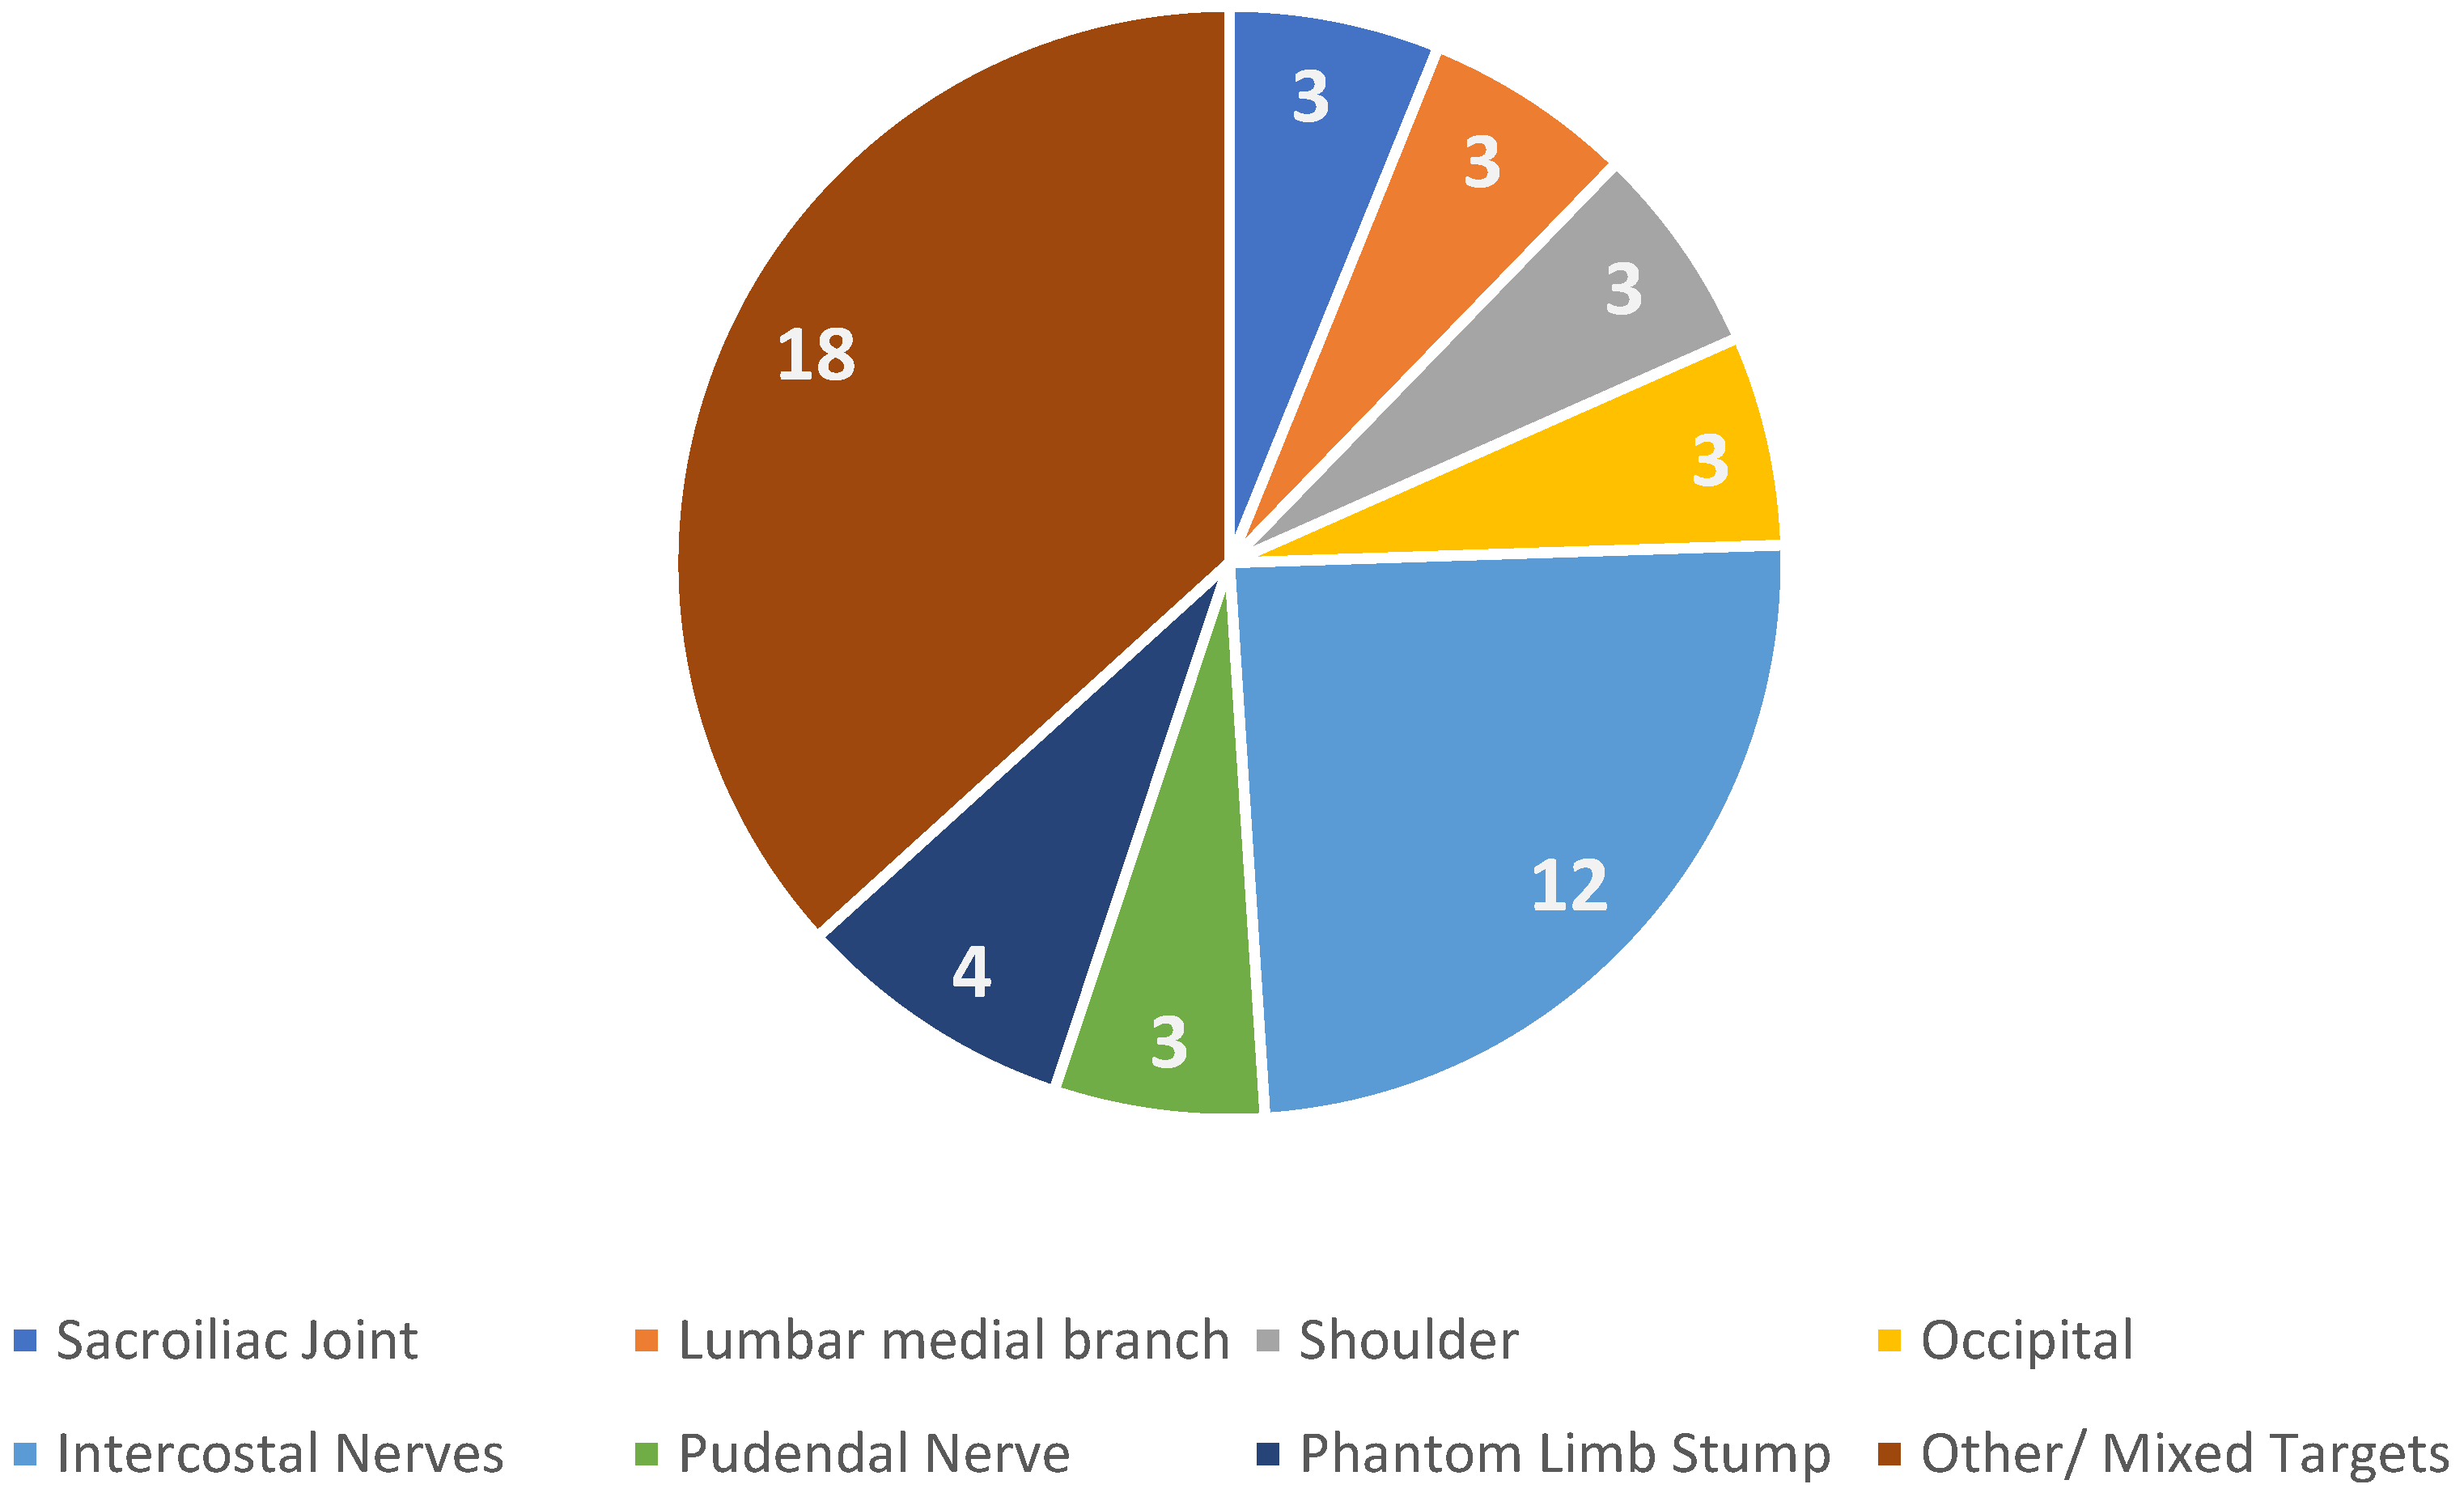

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Published by MDPI on behalf of the Lithuanian University of Health Sciences. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).