Systematic Review of Quantitative Metrics to Standardize Contours on Radiotherapy Clinical Trials


Simple Summary
Abstract
1. Introduction
2. Materials and Methods
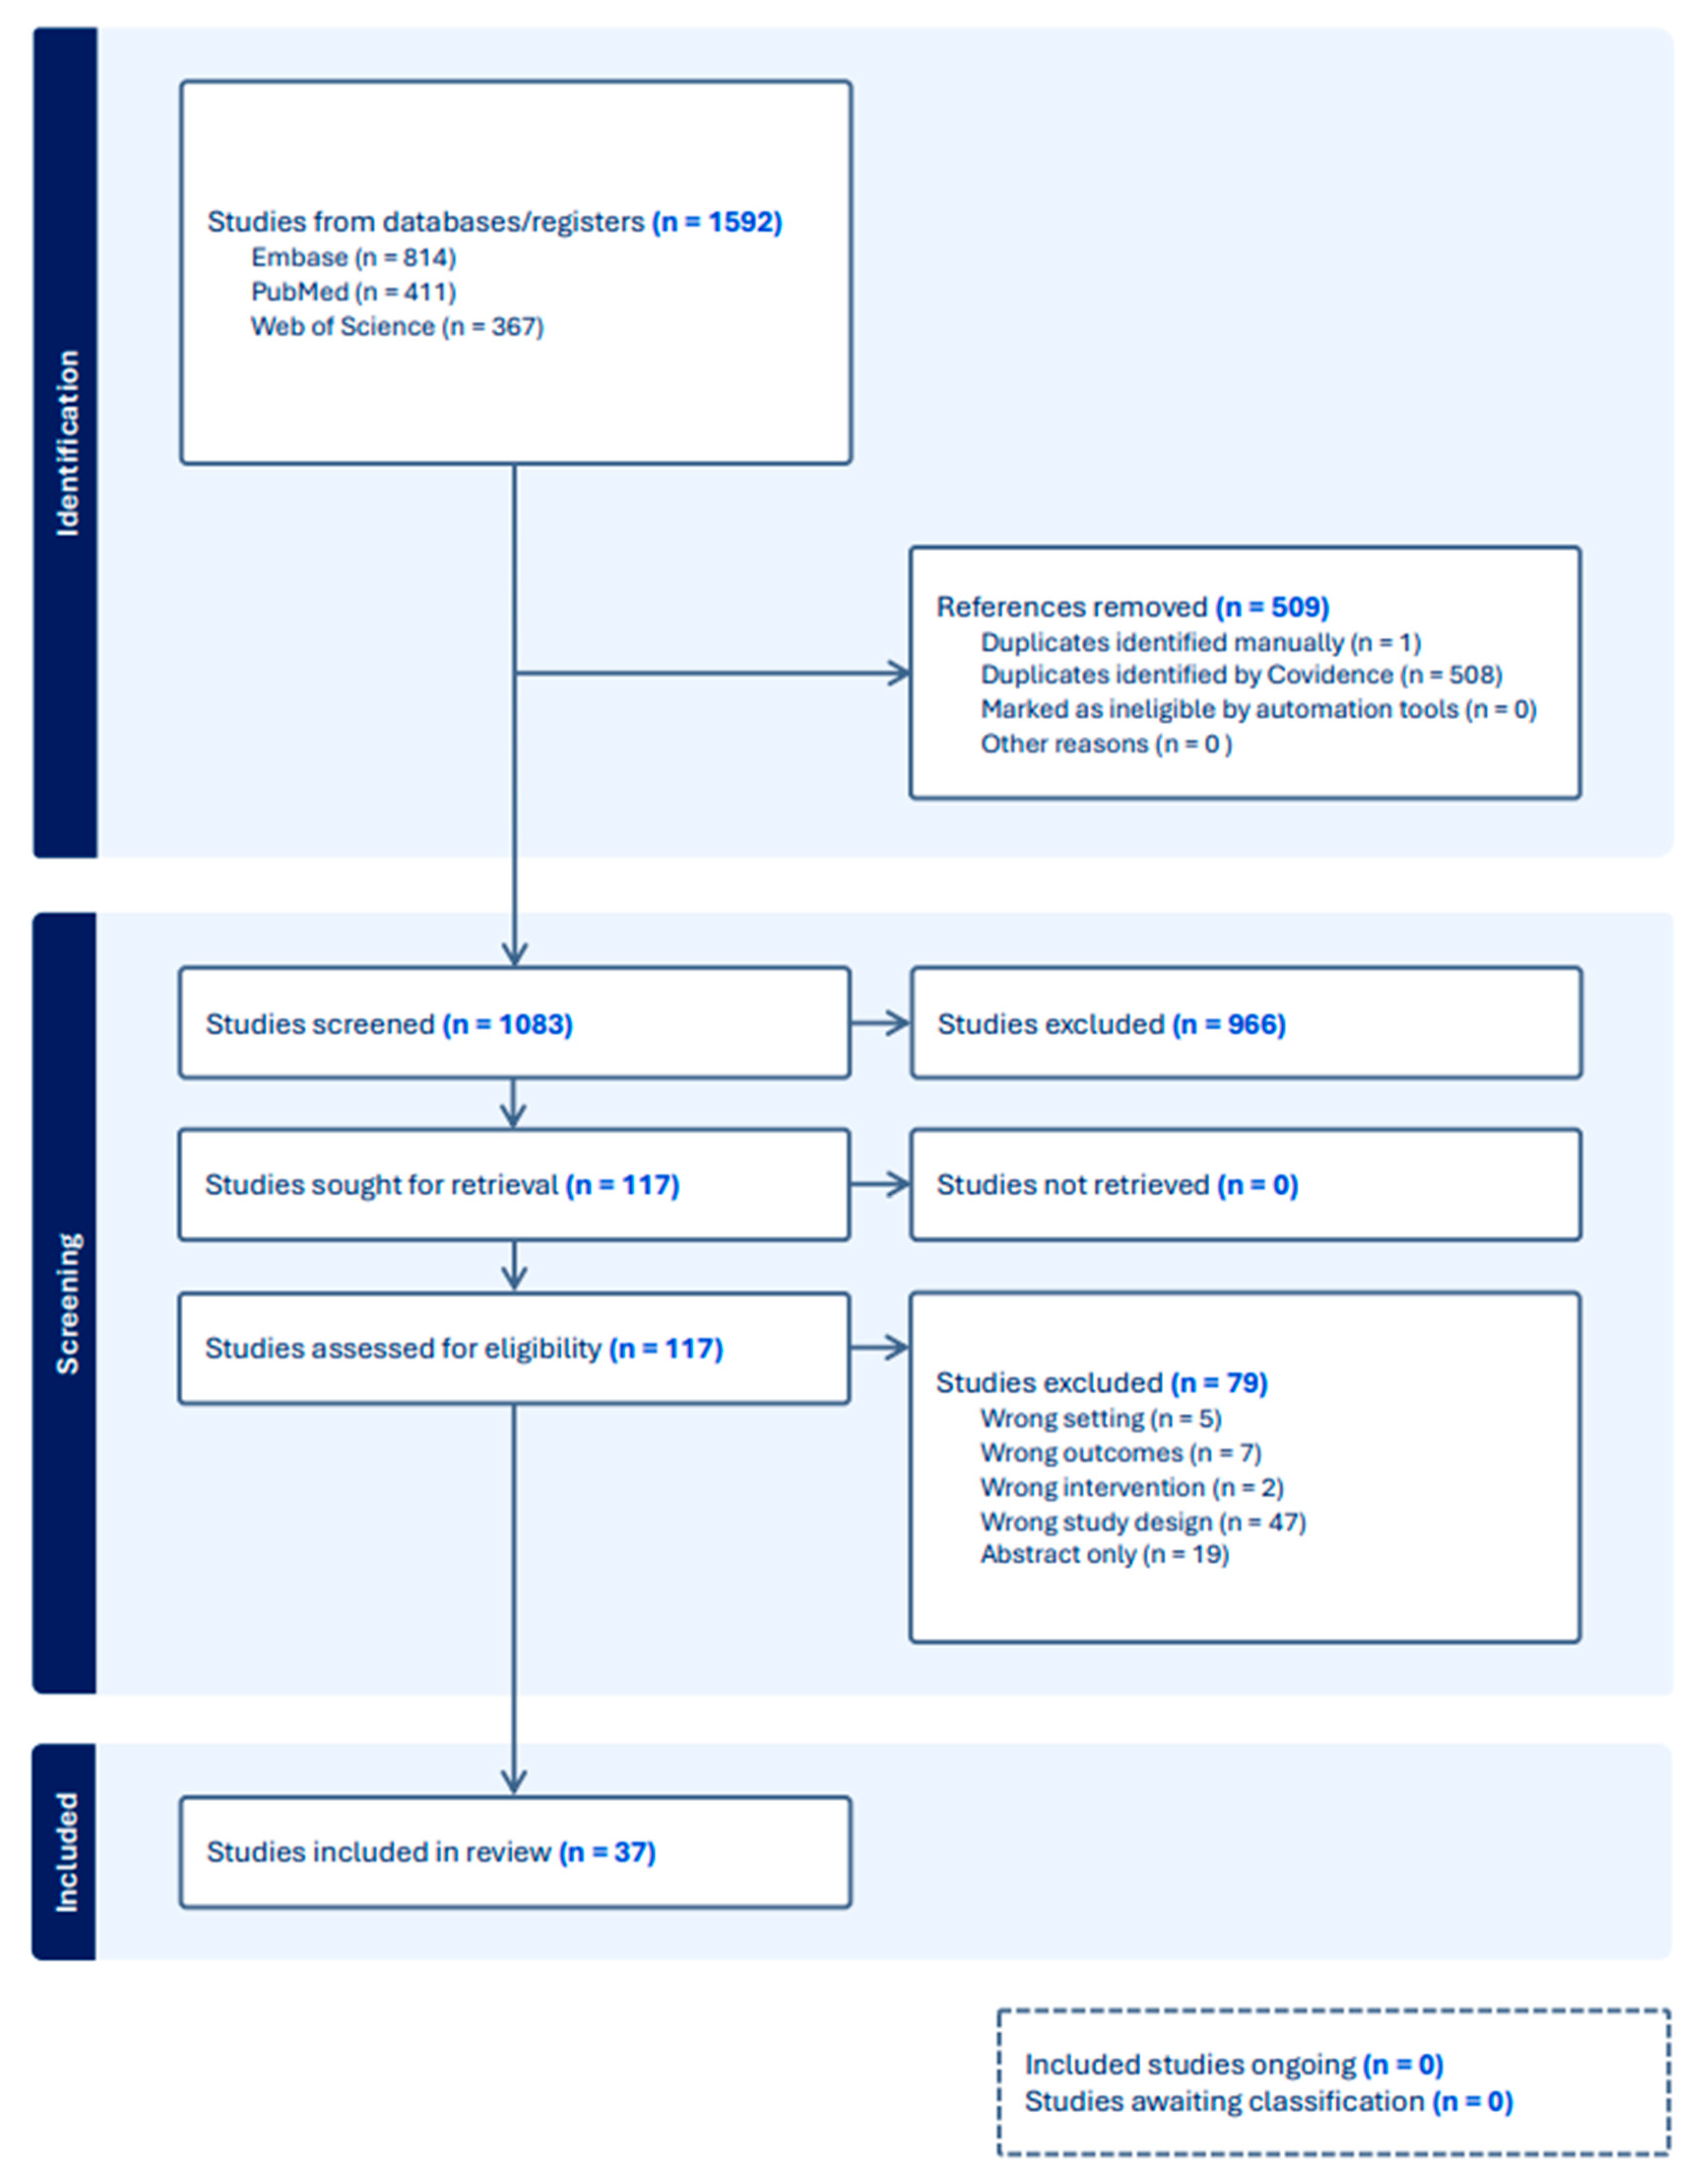
3. Results
3.1. Study Characteristics

| Author, year | Region | Disease Site | Study Type | Relevant Clinical Trial | QA Approach | Contour Evaluation Method | Quantitative Metrics Used | Key Findings |
|---|---|---|---|---|---|---|---|---|
| Mir, 2020 [46] | Multi-national | Multi-site | OAR Contouring Guideline Development for Clinical Trials | N/A | Global Quality Assurance of Radiation Therapy Clinical Trials Harmonization Group working group (GHG) review of OAR structures across clinical trials | Expert review | None reported | Consensus guidance on clinical trial OARs with peer-reviewed descriptions |
| Yang, 2020 [45] | Europe/ UK | Multi-site | OAR Contouring Guideline Development for Clinical Trials | NIHRCRN trials | Two-round Delphi assessment to determine OAR descriptions | Expert review | None reported | Consensus guidance on clinical trial OARs with peer-reviewed descriptions |
| Harmon, 2021 [47] | Europe/ UK | Prostate | Contouring guideline validation | LOCATE trial | Patterns of recurrence used to evaluate validity of contouring guidelines on trial | Expert review | None reported | Validated updated contouring guidelines |
| Mir, 2023 [35] | Europe/ UK | Lung | Retrospective case review | CONVERT Trial | Expert generated contours were compared to the patient contours | Expert review | None reported | Significant non-compliance was found with respect to OAR contours. |
| Haas, 2022 [36] | Europe/EORTC | Retroperitoneal sarcoma | Retrospective case review | EORTC 62092–22092 STRASS | Expert review of cases treated on trial | Expert review | None reported | Improved recurrence-free survival for patients treated without protocol non-compliance |
| Fairchild, 2012 [37] | Europe/EORTC | CNS | Retrospective case review | EORTC 22033–26033/NCIC CE5 Phase III | Expert review of cases treated on trial | Expert review | None reported | Significant protocol violations detected with respect to target volume and OAR contours |
| Toita, 2011 [38] | Japan/JGOG | Cervical | Retrospective case review | JGOG1066 | Expert review of cases treated on trial | Expert review | None reported | Radiotherapy protocol compliance was favorable except for the radiation boost indications |
| Beck, 2022 [39] | Europe/EORTC | Prostate | Retrospective case review | EORTC SAKK 09/10 | Expert review of cases treated on trial | Expert review | None reported | Significant protocol violations detected with respect to target volume and OAR contours |
| Abrunhosa-Branquinho, 2018 [40] | US/Europe/ RTOG/EORTC | CNS | Retrospective case review | RTOG 0834/EORTC 26053–22054/NCIC CTG CEC.1/ CATNON intergroup trial | Expert review of cases treated on trial | Expert review | None reported | Significant protocol violations detected, particularly for PTV delineation |
| Zhong, 2019 [41] | US/NRG/RTOG | HNSCC | Retrospective case review | NRG/RTOG 0522 | Expert review of cases treated on trial, correlated with clinical outcomes | Expert review | None reported | Local control was significantly different between the per-protocol and variation-acceptable patients in target and OAR contouring |
| Sanuki, 2009 [42] | Japan/JCOG | Lung | Retrospective case review | JCOG 0202 Phase III | Expert review of cases treated on trial | Expert review | None reported | Substantial contour violations reported |
| Schiff, 2023 [43] | US/ACNS | Peds/CNS | Retrospective case review | ACNS 0331 Phase III | Expert review of cases treated on trial, correlated with clinical outcomes. | Expert review | None reported | Substantial contour violations detected, but were not correlated with clinical outcomes |
| Fokas, 2016 [26] | Europe/ UK | Pancreas | Retrospective case review | SCALOP Trial | Expert review of cases treated on trial | Expert review with use of quantitative metrics | Jaccard Conformity Index (JCI) and Geographical Miss Index (GMI) used to compare accuracy of investigators’ GTV and PTV to trials team-defined gold standard | Substantial contour violations detected |
| Gwynne, 2012 [18] | UK | Esophagus | Retrospective case review | SCOPE 1 trial | Expert review of cases treated on trial | Expert review with use of quantitative metrics | Jaccard Conformity Index (JCI), Dice coefficient, van’t Riet index, Geographical Miss Index (GMI), and discordance index were used to compare GTV patient contours to expert contours | JCI was the most useful single metric to detect inter-observer variation in contours |
| Khaw, 2022 [44] | TROG | Endometrial | Retrospective case review | PORTEC-3 (TROG 08.04) | Expert review of cases treated on trial | Expert review | None reported | Authors found low rates of both minor and major deviations in contouring and dosimetry |
| Olch, 2023 [49] | Children’s Oncology Group | Peds/CNS | Computer program used to retrospectively review trial cases | ACNS 1123 | Commercially available plan quality scoring algorithm was used to create a scoring system using the protocol dosimetric requirements | Computer program | Points system (70 for PTV, 30 for OAR) | Objective scoring system used to evaluate plan quality |
| Thor, 2021 [48] | US/NRG/RTOG | Lung | AI program used to generate OAR contours | RTOG 0617 | Comparison of Artificial Intelligence (AI)-generated and MD-generated hearts | AI and Deep learning models | Computer generated deep learning model used to assess OAR heart contours | Trial heart doses were found to be significantly higher than previously reported, which may have led to an even more rapid mortality accumulation |
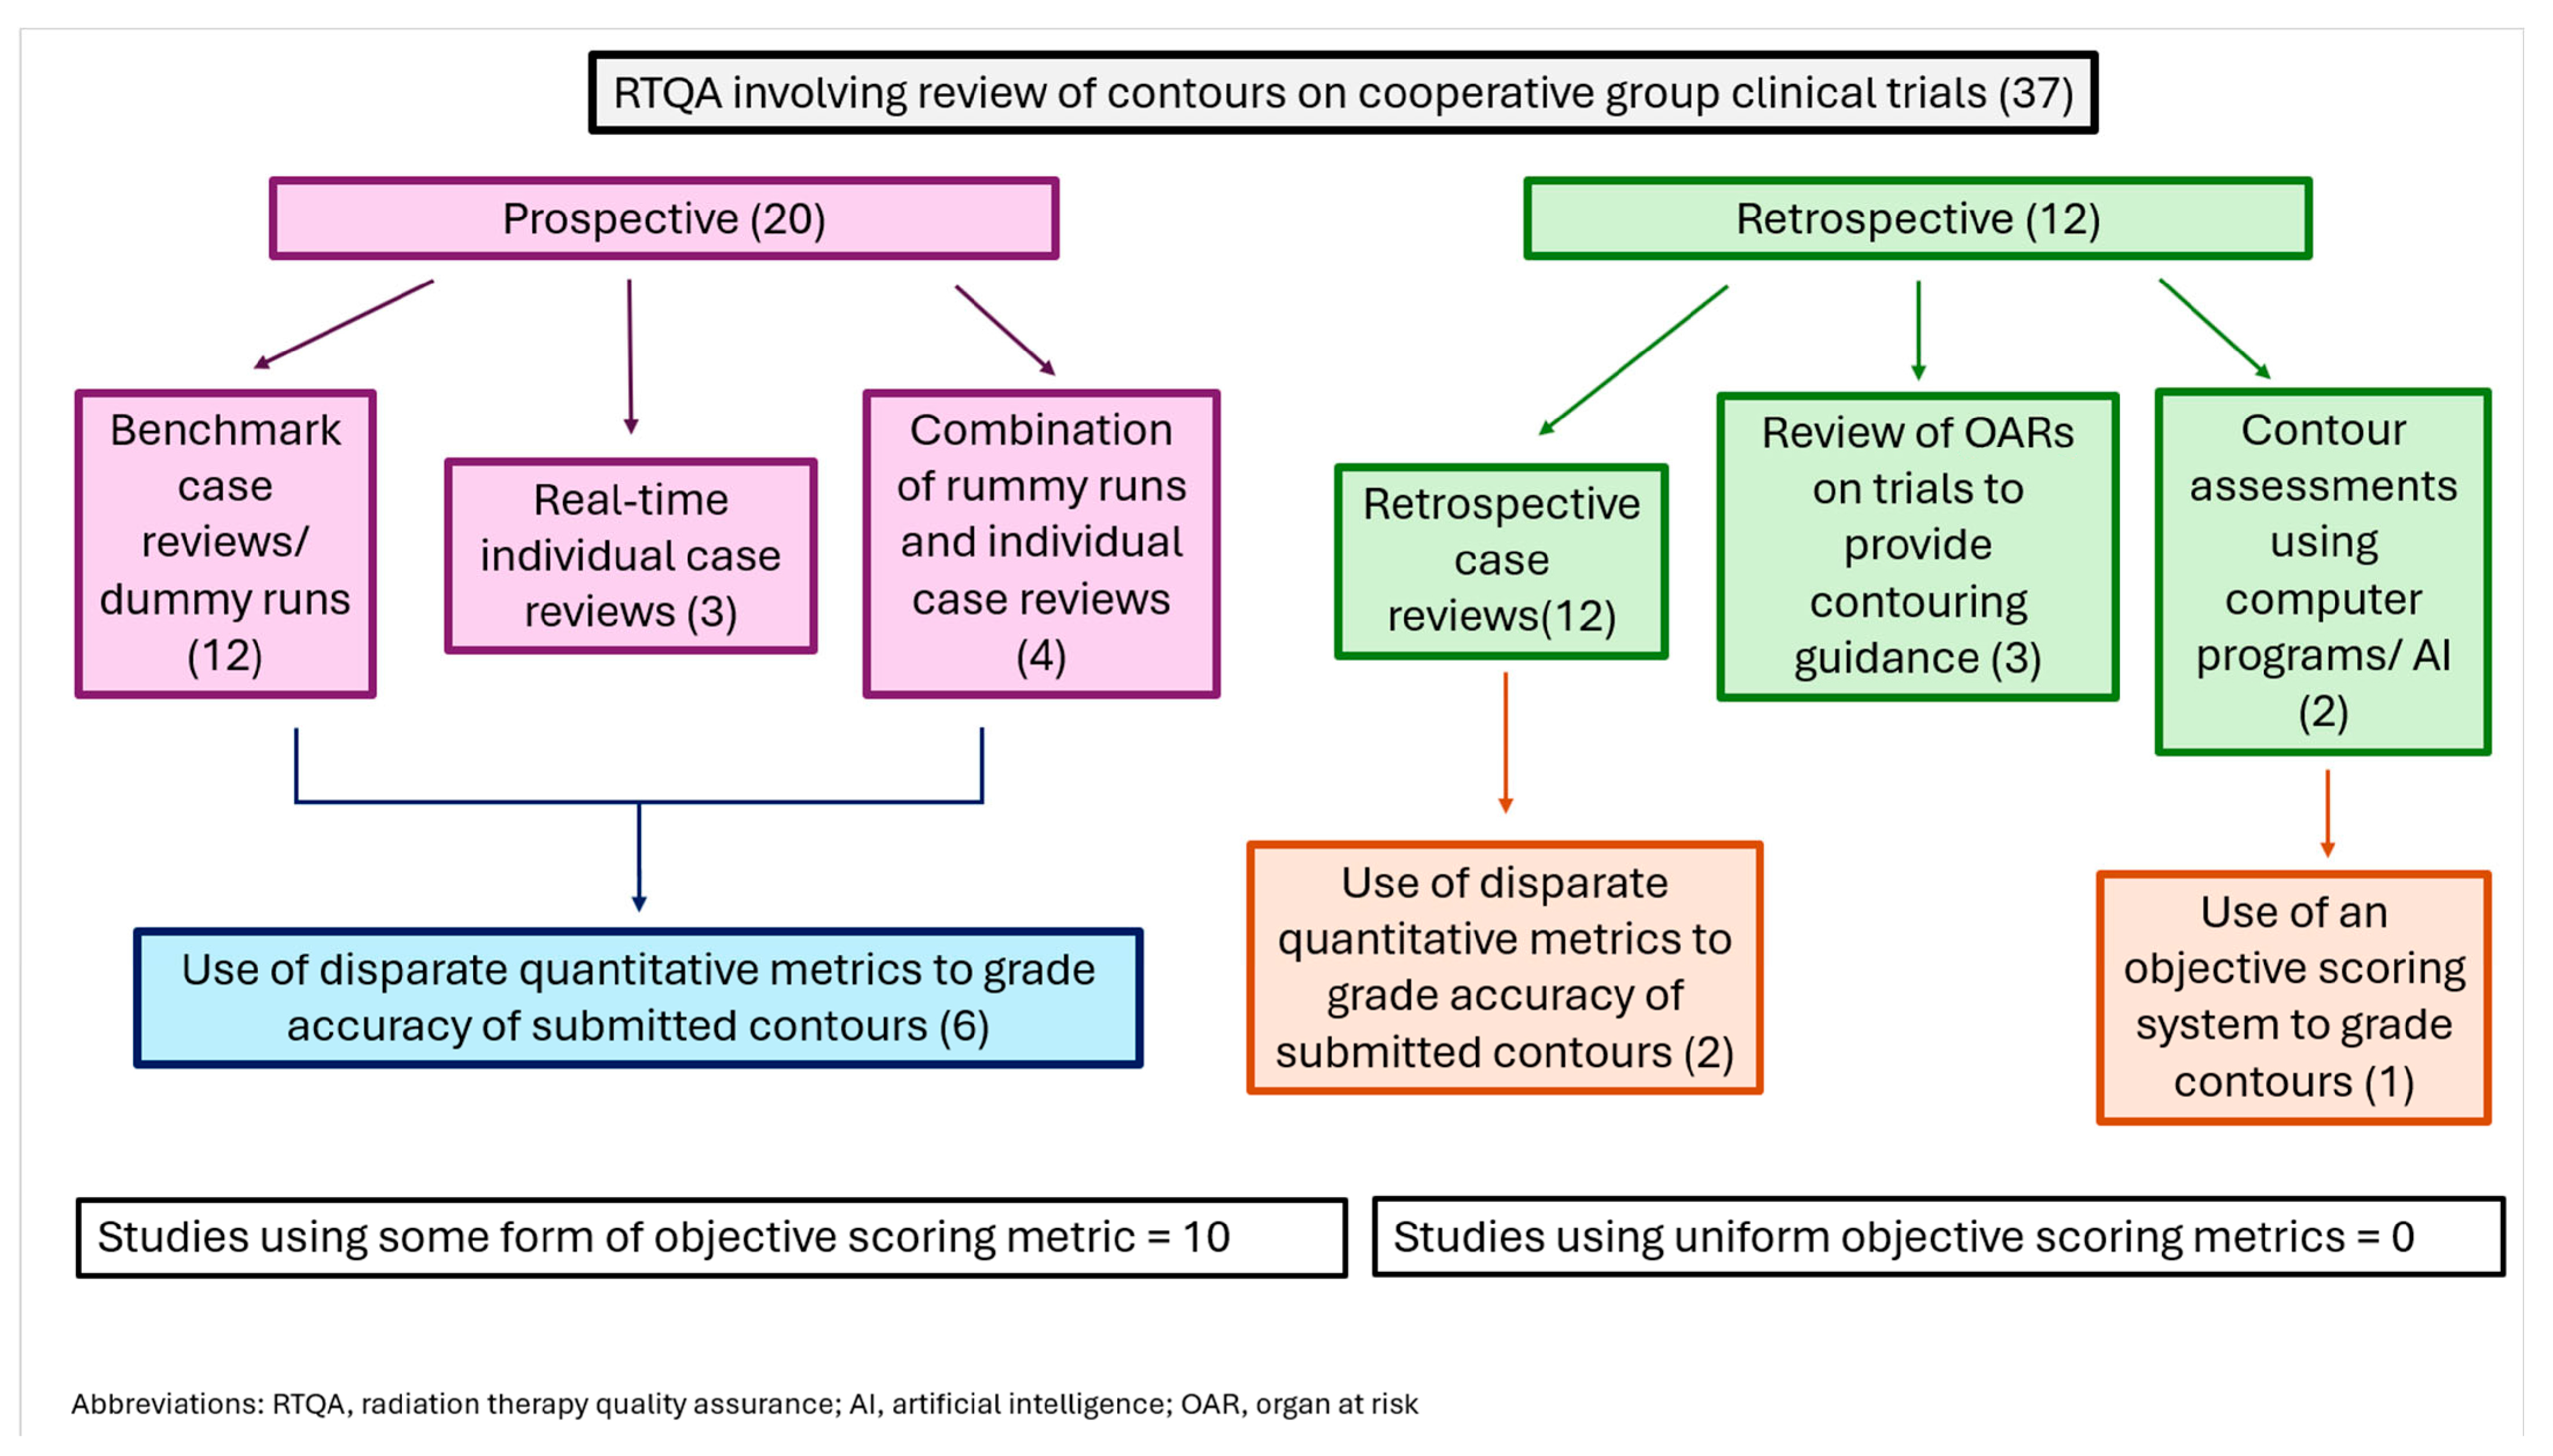
3.2. Thematic Synthesis of Findings
4. Discussion
Future Directions
5. Conclusions
Supplementary Materials
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Acknowledgments
Conflicts of Interest
Abbreviations
| RTQA | Radiation therapy quality assurance |
| RT | Radiation therapy |
References
- Delaney, G.; Jacob, S.; Featherstone, C.; Barton, M. The role of radiotherapy in cancer treatment. Cancer 2005, 104, 1129–1137. [Google Scholar] [CrossRef] [Scilit]
- Tchelebi, L.; Winter, K.; Abrams, R.; Safran, H.; Regine, W.; McNulty, S.; Wu, A.; Du, K.; Seaward, S.; Bian, S.; et al. Analysis of Radiation Therapy Quality Assurance in NRG Oncology RTOG 0848. Int. J. Radiat. Oncol. 2021, 111, S40. [Google Scholar] [CrossRef] [Scilit]
- Cox, S.; Cleves, A.; Clementel, E.; Miles, E.; Staffurth, J.; Gwynne, S. Impact of deviations in target volume delineation—Time for a new RTQA approach? Radiother. Oncol. 2019, 137, 1–8. [Google Scholar] [CrossRef] [Scilit]
- Ohri, N.; Shen, X.; Dicker, A.P.; Doyle, L.A.; Harrison, A.S.; Showalter, T.N. Radiotherapy Protocol Deviations and Clinical Outcomes: A Meta-analysis of Cooperative Group Clinical Trials. JNCI J. Natl. Cancer Inst. 2013, 105, 387–393. [Google Scholar] [CrossRef] [Scilit]
- Abrams, R.A.; Winter, K.A.; Regine, W.F.; Safran, H.; Hoffman, J.P.; Lustig, R.; Konski, A.A.; Benson, A.B.; Macdonald, J.S.; Rich, T.A.; et al. Failure to Adhere to Protocol Specified Radiation Therapy Guidelines Was Associated with Decreased Survival in RTOG 9704—A Phase III Trial of Adjuvant Chemotherapy and Chemoradiotherapy for Patients with Resected Adenocarcinoma of the Pancreas. Int. J. Radiat. Oncol. 2012, 82, 809–816. [Google Scholar] [CrossRef] [Scilit]
- Fairchild, A.; Straube, W.; Laurie, F.; Followill, D. Does Quality of Radiation Therapy Predict Outcomes of Multicenter Cooperative Group Trials? A Literature Review. Int. J. Radiat. Oncol. 2013, 87, 246–260. [Google Scholar] [CrossRef] [Scilit]
- Albert, J.M.; Das, P. Quality Indicators in Radiation Oncology. Int. J. Radiat. Oncol. 2013, 85, 904–911. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Balincourt, C.; Lacombe, D.; Coens, C.; Dulk, M.D.; Machiels, J.-P.; Weber, D.; Spahn, M.; Salgado, R.; Kasper, B.; Hau, P.; et al. Multidisciplinary quality assurance and control in oncological trials: Perspectives from European Organisation for Research and Treatment of Cancer (EORTC). Eur. J. Cancer 2017, 86, 91–100. [Google Scholar] [CrossRef] [Scilit]
- Bekelman, J.E.; Deye, J.A.; Vikram, B.; Bentzen, S.M.; Bruner, D.; Curran, W.J.; Dignam, J.; Efstathiou, J.A.; FitzGerald, T.; Hurkmans, C.; et al. Redesigning Radiotherapy Quality Assurance: Opportunities to Develop an Efficient, Evidence-Based System to Support Clinical Trials—Report of the National Cancer Institute Work Group on Radiotherapy Quality Assurance. Int. J. Radiat. Oncol. 2012, 83, 782–790. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McDowell, L.J.; Corry, J. A Call to Arms: Radiation Therapy Quality Assurance in the Next Generation of Clinical Trials. Int. J. Radiat. Oncol. 2018, 102, 1590–1591. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Corrigan, K.L.; Kry, S.; Howell, R.M.; Kouzy, R.; Jaoude, J.A.; Patel, R.R.; Jhingran, A.; Taniguchi, C.; Koong, A.C.; McAleer, M.F.; et al. The radiotherapy quality assurance gap among phase III cancer clinical trials. Radiother. Oncol. 2021, 166, 51–57. [Google Scholar] [CrossRef] [Scilit]
- Lin, D.; Lapen, K.; Sherer, M.V.; Kantor, J.; Zhang, Z.; Boyce, L.M.; Bosch, W.; Korenstein, D.; Gillespie, E.F. A Systematic Review of Contouring Guidelines in Radiation Oncology: Analysis of Frequency, Methodology, and Delivery of Consensus Recommendations. Int. J. Radiat. Oncol. 2020, 107, 827–835. [Google Scholar] [CrossRef] [Scilit]
- Wills, L.; Maggs, R.; Lewis, G.; Jones, G.; Nixon, L.; Staffurth, J.; Crosby, T. Quality assurance of the SCOPE 1 trial in oesophageal radiotherapy. Radiat. Oncol. 2017, 12, 179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stelmes, J.-J.; Vu, E.; Grégoire, V.; Simon, C.; Clementel, E.; Kazmierska, J.; Grant, W.; Ozsahin, M.; Tomsej, M.; Vieillevigne, L.; et al. Quality assurance of radiotherapy in the ongoing EORTC 1420 “Best of” trial for early stage oropharyngeal, supraglottic and hypopharyngeal carcinoma: Results of the benchmark case procedure. Radiat. Oncol. 2021, 16, 81. [Google Scholar] [CrossRef] [Scilit]
- Okamoto, H.; Murakami, N.; Isohashi, F.; Kasamatsu, T.; Hasumi, Y.; Iijima, K.; Nishioka, S.; Nakamura, S.; Nakamura, M.; Nishio, T.; et al. Dummy-run for standardizing plan quality of intensity-modulated radiotherapy for postoperative uterine cervical cancer: Japan Clinical Oncology Group study (JCOG1402). Radiat. Oncol. 2019, 14, 133. [Google Scholar] [CrossRef] [Scilit]
- Musat, E.; Roelofs, E.; Bar-Deroma, R.; Fenton, P.; Gulyban, A.; Collette, L.; Stupp, R.; Weber, D.C.; Davis, J.B.; Aird, E.; et al. Dummy run and conformity indices in the ongoing EORTC low-grade glioma trial 22033-26033: First evaluation of quality of radiotherapy planning. Radiother. Oncol. 2010, 95, 218–224. [Google Scholar] [CrossRef] [Scilit]
- Gondi, V.; Cui, Y.; Mehta, M.P.; Manfredi, D.; Xiao, Y.; Galvin, J.M.; Rowley, H.; Tome, W.A. Real-Time Pretreatment Review Limits Unacceptable Deviations on a Cooperative Group Radiation Therapy Technique Trial: Quality Assurance Results of RTOG 0933. Int. J. Radiat. Oncol. 2015, 91, 564–570. [Google Scholar] [CrossRef] [Scilit]
- Gwynne, S.; Spezi, E.; Wills, L.; Nixon, L.; Hurt, C.; Joseph, G.; Evans, M.; Griffiths, G.; Crosby, T.; Staffurth, J. Toward Semi-automated Assessment of Target Volume Delineation in Radiotherapy Trials: The SCOPE 1 Pretrial Test Case. Int. J. Radiat. Oncol. 2012, 84, 1037–1042. [Google Scholar] [CrossRef] [Scilit]
- Christiaens, M.; Collette, S.; Overgaard, J.; Gregoire, V.; Kazmierska, J.; Castadot, P.; Giralt, J.; Grant, W.; Tomsej, M.; Bar-Deroma, R.; et al. Quality assurance of radiotherapy in the ongoing EORTC 1219-DAHANCA-29 trial for HPV/p16 negative squamous cell carcinoma of the head and neck: Results of the benchmark case procedure. Radiother. Oncol. 2017, 123, 424–430. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fairchild, A.; Langendijk, J.A.; Nuyts, S.; Scrase, C.; Tomsej, M.; Schuring, D.; Gulyban, A.; Ghosh, S.; Weber, D.C.; Budach, W. Quality assurance for the EORTC 22071–26071 study: Dummy run prospective analysis. Radiat. Oncol. 2014, 9, 248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lambrecht, M.; Clementel, E.; Sonke, J.-J.; Nestle, U.; Adebahr, S.; Guckenberger, M.; Andratschke, N.; Weber, D.C.; Verheij, M.; Hurkmans, C.W. Radiotherapy quality assurance of SBRT for patients with centrally located lung tumours within the multicentre phase II EORTC Lungtech trial: Benchmark case results. Radiother. Oncol. 2019, 132, 63–69. [Google Scholar] [CrossRef] [Scilit]
- Fokas, E.; Clifford, C.; Spezi, E.; Joseph, G.; Branagan, J.; Hurt, C.; Nixon, L.; Abrams, R.; Staffurth, J.; Mukherjee, S. Comparison of investigator-delineated gross tumor volumes and quality assurance in pancreatic cancer: Analysis of the pretrial benchmark case for the SCALOP trial. Radiother. Oncol. 2015, 117, 432–437. [Google Scholar] [CrossRef] [Scilit]
- Sassowsky, M.; Gut, P.; Hölscher, T.; Hildebrandt, G.; Müller, A.-C.; Najafi, Y.; Kohler, G.; Kranzbühler, H.; Guckenberger, M.; Zwahlen, D.R.; et al. Use of EORTC Target Definition Guidelines for Dose-Intensified Salvage Radiation Therapy for Recurrent Prostate Cancer: Results of the Quality Assurance Program of the Randomized Trial SAKK 09/10. Int. J. Radiat. Oncol. 2013, 87, 534–541. [Google Scholar] [CrossRef] [Scilit]
- Fenton, P.A.; Hurkmans, C.; Gulyban, A.; van der Leer, J.; Matzinger, O.; Poortmans, P.; Collette, L.; Bolla, M. Quality assurance of the EORTC 22043-30041 trial in post-operative radiotherapy in prostate cancer: Results of the Dummy Run procedure. Radiother. Oncol. 2013, 107, 346–351. [Google Scholar] [CrossRef] [Scilit]
- Cloak, K.; Jameson, M.G.; Paneghel, A.; Wiltshire, K.; Kneebone, A.; Pearse, M.; Sidhom, M.; Tang, C.; Fraser-Browne, C.; Holloway, L.C.; et al. Contour variation is a primary source of error when delivering post prostatectomy radiotherapy: Results of the Trans-Tasman Radiation Oncology Group 08.03 Radiotherapy Adjuvant Versus Early Salvage (RAVES) benchmarking exercise. J. Med. Imaging Radiat. Oncol. 2019, 63, 390–398. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fokas, E.; Spezi, E.; Patel, N.; Hurt, C.; Nixon, L.; Chu, K.; Joseph, G.; Staffurth, J.; Abrams, R.; Mukherjee, S. P-222 Analysis of tumour contours and radiotherapy planning of “on-trial” patients undergoing chemoradiotherapy (CRT) in SCALOP trial: Does pre-trial Radiotherapy Quality Assurance (RTQA) improve the quality of “on-trial” radiotherapy? Ann. Oncol. 2016, 27, ii64–ii65. [Google Scholar] [CrossRef] [Scilit]
- Matzinger, O.; Poortmans, P.; Giraud, J.-Y.; Maingon, P.; Budiharto, T.; Bergh, A.C.M.V.D.; Davis, J.B.; Musat, E.; Ataman, F.; Huyskens, D.P.; et al. Quality assurance in the 22991 EORTC ROG trial in localized prostate cancer: Dummy run and individual case review. Radiother. Oncol. 2009, 90, 285–290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kearvell, R.; Haworth, A.; Ebert, M.A.; Murray, J.; Hooton, B.; Richardson, S.; Joseph, D.J.; Lamb, D.; Spry, N.A.; Duchesne, G.; et al. Quality improvements in prostate radiotherapy: Outcomes and impact of comprehensive quality assurance during the TROG 03.04 ‘RADAR’ trial. J. Med. Imaging Radiat. Oncol. 2013, 57, 247–257. [Google Scholar] [CrossRef] [Scilit]
- Corry, J.; Moore, A.; Kenny, L.; Wratten, C.; Fua, T.; Lin, C.; Porceddu, S.; Liu, C.; Ruemelin, M.; Sharkey, A.; et al. Radiotherapy quality assurance in the TROG 12.01 randomised trial and its impact on loco-regional failure. Front. Oncol. 2024, 13, 1333098. [Google Scholar] [CrossRef] [Scilit]
- Okamoto, H.; Murakami, N.; Isohashi, F.; Kasamatsu, T.; Hasumi, Y.; Kobayashi, H.; Ishikawa, M.; Nakamura, M.; Nishio, T.; Igaki, H.; et al. Plan quality association between dummy run and individual case review in a prospective multi-institutional clinical trial of postoperative cervical cancer patients treated with intensity-modulated radiotherapy: Japan clinical Oncology Group study (JCOG1402). Radiother. Oncol. 2023, 183, 109630. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hardcastle, N.; Cook, O.; Ray, X.; Moore, A.; Moore, K.L.; Pryor, D.; Rossi, A.; Foroudi, F.; Kron, T.; Siva, S. Personalising treatment plan quality review with knowledge-based planning in the TROG 15.03 trial for stereotactic ablative body radiotherapy in primary kidney cancer. Radiat. Oncol. 2021, 16, 142. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tchelebi, L.T.; Winter, K.A.; Abrams, R.A.; Safran, H.P.; Regine, W.F.; McNulty, S.; Wu, A.; Du, K.L.; Seaward, S.A.; Bian, S.X.; et al. Analysis of Radiation Therapy Quality Assurance in NRG Oncology RTOG 0848. Int. J. Radiat. Oncol. 2023, 118, 107–114. [Google Scholar] [CrossRef] [Scilit]
- Lukovic, J.; Moore, A.J.; Lee, M.T.; Willis, D.; Ahmed, S.; Akra, M.; Hortobagyi, E.; Kron, T.; Joon, D.L.; Liu, A.; et al. The Feasibility of Quality Assurance in the TOPGEAR International Phase 3 Clinical Trial of Neoadjuvant Chemoradiation Therapy for Gastric Cancer (an Intergroup Trial of the AGITG/TROG/NHMRC CTC/EORTC/CCTG). Int. J. Radiat. Oncol. 2023, 117, 1096–1106. [Google Scholar] [CrossRef] [Scilit]
- Trada, Y.; Kneebone, A.; Paneghel, A.; Pearse, M.; Sidhom, M.; Tang, C.; Wiltshire, K.; Haworth, A.; Fraser-Browne, C.; Martin, J. Optimizing Radiation Therapy Quality Assurance in Clinical Trials: A TROG 08.03 RAVES Substudy. Int. J. Radiat. Oncol. 2015, 93, 1045–1051. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mir, R.; Groom, N.; Mistry, H.B.; Wilson, E.; Faivre-Finn, C. Association between radiotherapy protocol variations and outcome in the CONVERT trial. Clin. Transl. Radiat. Oncol. 2022, 39, 100560. [Google Scholar] [CrossRef] [Scilit]
- Haas, R.; Stelmes, J.; Zaffaroni, F.; Sauvé, N.; Clementel, E.; Bar-Deroma, R.; Le Péchoux, C.; Litière, S.; Marreaud, S.; Alyamani, N.; et al. Critical impact of radiotherapy protocol compliance and quality in the treatment of retroperitoneal sarcomas: Results from the EORTC 62092-22092 STRASS trial. Cancer 2022, 128, 2796–2805. [Google Scholar] [CrossRef] [Scilit]
- Fairchild, A.; Weber, D.C.; Bar-Deroma, R.; Gulyban, A.; Fenton, P.A.; Stupp, R.; Baumert, B.G. Quality assurance in the EORTC 22033–26033/CE5 phase III randomized trial for low grade glioma: The digital individual case review. Radiother. Oncol. 2012, 103, 287–292. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toita, T.; Kato, S.; Ishikura, S.; Tsujino, K.; Kodaira, T.; Uno, T.; Hatano, K.; Sakurai, H.; Niibe, Y.; Kazumoto, T.; et al. Radiotherapy quality assurance of the Japanese Gynecologic Oncology Group study (JGOG1066): A cooperative phase II study of concurrent chemoradiotherapy for uterine cervical cancer. Int. J. Clin. Oncol. 2011, 16, 379–386. [Google Scholar] [CrossRef] [Scilit]
- Beck, M.; Sassowsky, M.; Schär, S.; Mathier, E.; Halter, M.; Zwahlen, D.R.; Hölscher, T.; Arnold, W.; Polat, B.; Hildebrandt, G.; et al. Adherence to Contouring and Treatment Planning Requirements Within a Multicentric Trial: Results of the Quality Assurance of the SAKK 09/10 trial. Int. J. Radiat. Oncol. 2022, 113, 80–91. [Google Scholar] [CrossRef] [Scilit]
- Abrunhosa-Branquinho, A.N.; Bar-Deroma, R.; Collette, S.; Clementel, E.; Liu, Y.; Hurkmans, C.W.; Feuvret, L.; Van Beek, K.; Bent, M.v.D.; Baumert, B.G.; et al. Radiotherapy quality assurance for the RTOG 0834/EORTC 26053-22054/NCIC CTG CEC.1/CATNON intergroup trial “concurrent and adjuvant temozolomide chemotherapy in newly diagnosed non-1p/19q deleted anaplastic glioma”: Individual case review analysis. Radiother. Oncol. 2018, 127, 292–298. [Google Scholar] [CrossRef] [Scilit]
- Zhong, H.; Men, K.; Wang, J.; van Soest, J.; Rosenthal, D.; Dekker, A.; Zhang, Z.; Xiao, Y. The Impact of Clinical Trial Quality Assurance on Outcome in Head and Neck Radiotherapy Treatment. In Proceedings of the 59th Annual Scientific Meeting of the American-Society-for-Radiation-Oncology (ASTRO), San Diego, CA, USA, 24–27 September 2017; p. 792. [Google Scholar]
- Sanuki-Fujimoto, N.; Ishikura, S.; Hayakawa, K.; Kubota, K.; Nishiwaki, Y.; Tamura, T. Radiotherapy quality assurance review in a multi-center randomized trial of limited-disease small cell lung cancer: The Japan Clinical Oncology Group (JCOG) trial 0202. Radiat. Oncol. 2009, 4, 16. [Google Scholar] [CrossRef] [Scilit]
- Schiff, J.P.; Lee, Y.; Wang, Y.; Perkins, S.M.; Kessel, S.K.; Fitzgerald, T.J.; Larrier, N.A.; Michalski, J.M. An Analysis of Major Target Deviations in Craniospinal Irradiation Treatment Plans for Patients with Intermediate-Risk Medulloblastoma Within a Phase 3 Clinical Trial (Children’s Oncology Group Study ACNS0331). Adv. Radiat. Oncol. 2022, 8, 101083. [Google Scholar] [CrossRef] [Scilit]
- Khaw, P.; Do, V.; Lim, K.; Cunninghame, J.; Dixon, J.; Vassie, J.; Bailey, M.; Johnson, C.; Kahl, K.; Gordon, C.; et al. Radiotherapy Quality Assurance in the PORTEC-3 (TROG 08.04) Trial. Clin. Oncol. 2022, 34, 198–204. [Google Scholar] [CrossRef] [Scilit]
- Yang, H.; Mir, R.; Díez, P.; Tsang, Y.; Conibear, J.; Simões, R.; Cox, S.; Webster, A.; Nabi, Z.; Eaton, D.; et al. Provision of Organ at Risk Contouring Guidance in UK Radiotherapy Clinical Trials. Clin. Oncol. 2020, 32, e60–e66. [Google Scholar] [CrossRef] [Scilit]
- Mir, R.; Kelly, S.M.; Xiao, Y.; Moore, A.; Clark, C.H.; Clementel, E.; Corning, C.; Ebert, M.; Hoskin, P.; Hurkmans, C.W.; et al. Organ at risk delineation for radiation therapy clinical trials: Global Harmonization Group consensus guidelines. Radiother. Oncol. 2020, 150, 30–39. [Google Scholar] [CrossRef] [Scilit]
- Harmon, G.; Chan, D.; Lee, B.; Miller, C.; Gorbonos, A.; Gupta, G.; Quek, M.; Woods, M.; Savir-Baruch, B.; Harkenrider, M.M.; et al. Validating Modern NRG Oncology Pelvic Nodal and Groupe Francophone de Radiothérapie Urologique Prostate Bed Contouring Guidelines for Post-Prostatectomy Salvage Radiation: A Secondary Analysis of the LOCATE Trial. Int. J. Radiat. Oncol. 2021, 111, 1195–1203. [Google Scholar] [CrossRef] [Scilit]
- Thor, M.; Apte, A.; Haq, R.; Iyer, A.; LoCastro, E.; Deasy, J.O. Using Auto-Segmentation to Reduce Contouring and Dose Inconsistency in Clinical Trials: The Simulated Impact on RTOG 0617. Int. J. Radiat. Oncol. 2020, 109, 1619–1626. [Google Scholar] [CrossRef] [Scilit]
- Olch, A.J.; Gopalakrishnan, M.; Murphy, E.S.; MacDonald, S.M.; Hua, C.-H. Toward Systematic Assessment and Improvement of Radiation Therapy Plan Quality of Cooperative Group Trial Submissions: A Report From the Children’s Oncology Group. Pract. Radiat. Oncol. 2023, 13, e374–e382. [Google Scholar] [CrossRef] [Scilit]
- Brooks, C.; Miles, E.; Hoskin, P.J. Radiotherapy trial quality assurance processes: A systematic review. Lancet Oncol. 2024, 25, e104–e113. [Google Scholar] [CrossRef] [Scilit]
- Vinod, S.K.; Jameson, M.G.; Min, M.; Holloway, L.C. Uncertainties in volume delineation in radiation oncology: A systematic review and recommendations for future studies. Radiother. Oncol. 2016, 121, 169–179. [Google Scholar] [CrossRef] [Scilit]
- Sherer, M.V.; Lin, D.; Elguindi, S.; Duke, S.; Tan, L.-T.; Cacicedo, J.; Dahele, M.; Gillespie, E.F. Metrics to evaluate the performance of auto-segmentation for radiation treatment planning: A critical review. Radiother. Oncol. 2021, 160, 185–191. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taha, A.A.; Hanbury, A. Metrics for evaluating 3D medical image segmentation: Analysis, selection, and tool. BMC Med. Imaging 2015, 15, 29. [Google Scholar] [CrossRef] [Scilit]
- Nikolov, S.; Blackwell, S.; Zverovitch, A.; Mendes, R.; Livne, M.; De Fauw, J.; Patel, Y.; Meyer, C.; Askham, H.; Romera-Paredes, B.; et al. Clinically Applicable Segmentation of Head and Neck Anatomy for Radiotherapy: Deep Learning Algorithm Development and Validation Study. J. Med. Internet Res. 2021, 23, e26151. [Google Scholar] [CrossRef] [Scilit]
- Vaassen, F.; Hazelaar, C.; Vaniqui, A.; Gooding, M.; van der Heyden, B.; Canters, R.; van Elmpt, W. Evaluation of measures for assessing time-saving of automatic organ-at-risk segmentation in radiotherapy. Phys. Imaging Radiat. Oncol. 2020, 13, 1–6. [Google Scholar] [CrossRef] [Scilit]
- Brouwer, C.L.; Steenbakkers, R.J.H.M.; van den Heuvel, E.; Duppen, J.C.; Navran, A.; Bijl, H.P.; Chouvalova, O.; Burlage, F.R.; Meertens, H.; Langendijk, J.A.; et al. 3D Variation in delineation of head and neck organs at risk. Radiat. Oncol. 2012, 7, 32. [Google Scholar] [CrossRef] [Scilit]
- Brouwer, C.L.; Steenbakkers, R.J.; Bourhis, J.; Budach, W.; Grau, C.; Grégoire, V.; van Herk, M.; Lee, A.; Maingon, P.; Nutting, C.; et al. CT-based delineation of organs at risk in the head and neck region: DAHANCA, EORTC, GORTEC, HKNPCSG, NCIC CTG, NCRI, NRG Oncology and TROG consensus guidelines. Radiother. Oncol. 2015, 117, 83–90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cox, B.W.; Teckie, S.; Kapur, A.; Chou, H.; Potters, L. Prospective Peer Review in Radiation Therapy Treatment Planning: Long-Term Results From a Longitudinal Study. Pr. Radiat. Oncol. 2020, 10, e199–e206. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]

| Author, Year | Region | Disease Site | Study Type | Relevant Clinical Trial | QA Approach | Contour Evaluation Method | Quantitative Metrics Used | Key Findings |
|---|---|---|---|---|---|---|---|---|
| Wills, 2017 [13] | UK | Esophagus | Benchmark Case/ Dummy Run | SCOPE 1 trial | Comparison to protocol reference standard | Expert review | None reported | Substantial variability in contours despite existence of a comprehensive protocol |
| Stelmes, 2021 [14] | Europe/ EORTC | Head and Neck | Benchmark Case/ Dummy Run | EORTC 1420 | Comparison to gold standard expert delineation | Expert review | None reported | OAR volume delineations were the cause for protocol failure in 53% of cases |
| Okamoto, 2019 [15] | Japan/ JCOG | Cervix | Benchmark Case/ Dummy Run | JCOG1402 | Comparison to protocol reference standard | Expert review | The Dice similarity coefficient (DSC) and the Hausdorff distance (HD) were calculated to assess inter-observer variability for delineation in the CTV and scored categorically (per protocol/acceptable variation/unacceptable) | Substantial variability in contours despite existence of a comprehensive protocol |
| Musat, 2010 [16] | Europe/ EORTC | CNS | Benchmark Case/ Dummy Run | EORTC 22033–26033 | Comparison to protocol reference standard | Expert review | None reported | Only two (5%) centers had to repeat target volume delineations |
| Gondi, 2015 [17] | US/NRG/ RTOG | CNS | Benchmark Case/ Dummy Run | RTOG 0933 | Comparison to gold standard expert delineation | Expert review with use of quantitative metrics | Hausdorff distance was calculated for the submitted hippocampal contour and scored categorically (per protocol/acceptable variation/unacceptable) | Real-time contour review limits unacceptable deviations |
| Christiaens, 2017 [19] | Europe/ EORTC | HNSCC | Benchmark Case/ Dummy Run | EORTC 1219-DAHANCA-29 | Comparison to gold standard expert delineation | Expert review with use of quantitative metrics | The Sørensen–Dice Similarity Index and the Hausdorff distance were calculated retrospectively and used to evaluate the overlap between the participating center’s delineations of CTVs and the expert contours | Contour delineation remains primary reason for protocol deviations |
| Fairchild, 2014 [20] | Europe/ EORTC | HNSCC | Benchmark Case/ Dummy Run | EORTC 22071–26071 | Comparison to gold standard expert delineation | Expert review | None reported | Substantial variability in contours despite existence of a comprehensive protocol |
| Lambrecht, 2019 [21] | Europe/ EORTC | Lung | Benchmark Case/ Dummy Run | EORTC Lungtech Trial | Comparison to protocol reference standard | Expert review | None reported | Contour delineation remains primary reason for protocol deviations |
| Fokas, 2015 [22] | Europe/ UK | Pancreas | Benchmark Case/ Dummy Run | SCALOP Trial | Comparison to gold standard expert delineation | Expert review with use of quantitative metrics | Whole-volume Jaccard Conformity Index (JCI) and Geographic Miss Index (GMI) were generated for both GTV and PTV comparison. JCI is defined as the volume of the gold standard contour encompassed by the investigator contour as a fraction of their combined volume. | There was considerable variation in GTV delineation |
| Sassowsky, 2013 [23] | Europe | Prostate | Benchmark Case/ Dummy Run | SAKK 09/10 | Comparison to protocol reference standard | Expert review with use of quantitative metrics | Inter-observer agreement on target volume and OAR delineation was assessed by the apparent volume overlap, which was corrected for agreement by chance using Fleiss’ κ | Substantial variability in contours on first attempt despite existence of a comprehensive protocol |
| Fenton, 2013 [24] | Europe/ EORTC | Prostate | Benchmark Case/ Dummy Run | EORTC 22043–30041 | Comparison to protocol reference standard | Expert review | None reported | Substantial variability in contours despite existence of a comprehensive protocol |
| Cloak, 2019 [25] | TROG | Prostate | Benchmark Case/ Dummy Run | TROG 08.03 RAVES | Comparison to protocol reference standard | Expert review with use of quantitative metrics | Quantitative geometric parameters including volume, Hausdorff distance (HD), mean distance to agreement (MDA) and Dice similarity coefficient (DSC) were analyzed for targets and organs at risk. | Variability was found most notably in CTV and rectum delineation as a primary source of protocol error. |
| Matzinger, 2009 [27] | Europe/ EORTC | Prostate | Benchmark Case/ Dummy Run + Individual case review | EORTC 22991 | Comparison to protocol reference standard | Expert review | None reported | Volume delineation varied significantly between investigators; however, no major protocol deviations were observed in individual case reviews |
| Kearvell, 2013 [28] | TROG | Prostate | Benchmark Case/ Dummy Run + Individual case review | TROG 03.04 ‘RADAR’ | Comparison to protocol reference standard | Expert review | None reported | Substantial variability in contours despite existence of a comprehensive protocol |
| Corry, 2024 [29] | TROG | Head and Neck | Benchmark Case/ Dummy Run + Individual case review + post-treatment RTQA review | TROG 12.01 | Comparison to protocol reference standard | Expert review | None reported | Major protocol deviations were found indicating importance of pre-treatment RTQA |
| Okamoto, 2023 [30] | Japan/ JCOG | Cervix | Benchmark Case/ Dummy Run + post-treatment RTQA review | JCOG1402 | Comparison to gold standard expert delineation | Expert review with use of quantitative metrics | None reported | Frequent deviations were observed in clinical target volume (CTV) delineations |
| Hardcastle, 2021 [31] | TROG | Kidney | Prospective real-time individual case review | TROG 15.03 FASTRACK II | Comparison to protocol reference standard | Expert review | None reported (Note: KBP modeling was used for plan and DVH review but not contour review) | Real time plan review can improve treatment plan quality |
| Tchelebi, 2024 [32] | US/NRG/RTOG | Pancreas | Prospective real-time individual case review | RTOG 0848 Phase III | Comparison to protocol reference standard | Expert review | None reported | Substantial variability in contours despite existence of a comprehensive protocol |
| Lukovic, 2023 [33] | International: AGITG, TROG, EORTC, CCTG | Gastric | Prospective real-time individual case review | TOPGEAR International Phase III | Comparison to protocol reference standard | Expert review | None reported | Substantial variability in CTV contours despite existence of a comprehensive protocol |
| Trada, 2015 [34] | TROG | Prostate | Prospective real-time individual case review | TROG 08.03 RAVES | Comparison to protocol reference standard | Expert review | None reported | The majority of protocol deviations were due to contouring and dosimetric violations |
| Contour Evaluation Method | Number of Studies (%) |
|---|---|
| Expert review only | 26 (70) |
| Expert review with use of quantitative metrics | 6 (16) |
| AI-assisted contour review | 1 (3) |
| Computer based objective scoring system for contour review | 1 (3) |
| Study | Year | Disease Site | Metric(s) Used | Thresholds Defined? | Application | Key Finding |
|---|---|---|---|---|---|---|
| Gwynne et al. [18] | 2012 | Esophageal | Volume overlap, DSC, conformity index | No | Research analysis of benchmark | Median DSC 0.67 for GTV; high variability |
| Sassowsky et al. [23] | 2013 | Prostate | Conformity index, volume comparison | No | Benchmark case assessment | Substantial volume differences vs. reference |
| Gondi et al. [17] | 2015 | Brain | Visual comparison with quantitative volumetric analysis | No | Real-time review | 35% unacceptable deviations initially |
| Fokas et al. [26] | 2016 | Pancreatic | DSC, volume ratios | No | Retrospective analysis | DSC range 0.48–0.85; no correlation with protocol adherence |
| Christiaens et al. [19] | 2017 | Head & Neck | Volume, DSC | No | Benchmark assessment | Delineation primary deviation cause |
| Okamoto et al. [15] | 2019 | Cervical | Volumetric comparison, distance metrics | No | Dummy run standardization | Improved consistency after feedback |
| Cloak et al. [25] | 2019 | Prostate | Volume analysis, spatial comparison | No | Benchmark (RAVES trial) | Contour variation primary error source |
| Thor et al. [48] | 2021 | Lung | Auto-segmentation comparison | No | Retrospective reanalysis | Heart doses underestimated due to contour inconsistency |
| Okamoto et al. [30] | 2023 | Cervical | Volume metrics | No | Individual case review correlation with dummy run | Association between dummy run and on-trial performance |
| Olch et al. [49] | 2023 | CNS | Comprehensive scoring system | Yes | Plan quality assessment | Only study with objective scoring thresholds |
| Time Period | Total Studies | Qualitative Expert Review Only | Quantitative Metrics Used | Objective Scoring System | Predominant Approach |
|---|---|---|---|---|---|
| 2009–2013 | 8 | 7 (88%) | 1 (12%) | 0 (0%) | Gold standard comparison, qualitative |
| 2014–2017 | 11 | 8 (73%) | 3 (27%) | 0 (0%) | Expert review with emerging metrics |
| 2018–2021 | 10 | 6 (60%) | 4 (40%) | 0 (0%) | Mixed qualitative/quantitative |
| 2022–2024 | 8 | 4 (50%) | 3 (38%) | 1 (12%) | Increasing quantification |
| QA Type | Number of Studies | Studies Using Quantitative Metrics | Percentage |
|---|---|---|---|
| Dummy Run/Benchmark Only | 12 | 6 | 50% |
| Individual Case Review (Prospective) | 8 | 0 | 0% |
| Individual Case Review (Retrospective) | 12 | 3 | 25% |
| Combined Dummy Run + Individual Review | 5 | 1 | 20% |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Tchelebi, L.T.; Lester, J.; Kim, J.J.; Geng, H.; Xiao, Y. Systematic Review of Quantitative Metrics to Standardize Contours on Radiotherapy Clinical Trials. Radiation 2026, 6, 20. https://doi.org/10.3390/radiation6020020
Tchelebi LT, Lester J, Kim JJ, Geng H, Xiao Y. Systematic Review of Quantitative Metrics to Standardize Contours on Radiotherapy Clinical Trials. Radiation. 2026; 6(2):20. https://doi.org/10.3390/radiation6020020
Chicago/Turabian StyleTchelebi, Leila T., Janice Lester, Joshua J. Kim, Huaizhi Geng, and Ying Xiao. 2026. "Systematic Review of Quantitative Metrics to Standardize Contours on Radiotherapy Clinical Trials" Radiation 6, no. 2: 20. https://doi.org/10.3390/radiation6020020
APA StyleTchelebi, L. T., Lester, J., Kim, J. J., Geng, H., & Xiao, Y. (2026). Systematic Review of Quantitative Metrics to Standardize Contours on Radiotherapy Clinical Trials. Radiation, 6(2), 20. https://doi.org/10.3390/radiation6020020