


Abstract
Background/Objectives: Artificial intelligence (AI) is increasingly proposed to improve surgical planning, guidance, and postoperative surveillance. Yet many promising applications remain disconnected from the full surgical pathway and the feasible limitations of clinical deployment. In contrast to prior reviews that primarily catalog AI use cases, this review combines the literature to define the translational pathway—from label design through staged validation to workflow integration—required for clinically deployable computed tomography (CT)-based surgical AI. CT and particularly computed tomography angiography (CTA) are especially usable sources for surgical AI because they provide a standardized three-dimensional anatomic model that is already embedded in many clinical workflows. In autologous breast reconstruction, deep inferior epigastric perforator (DIEP) flap CTA offers an unusually strong model system: the anatomy is discrete, surgeon decisions are actionable, and downstream operative and postoperative outcomes are measurable. These characteristics make DIEP reconstruction suitable not only for technical model development, but also for exacting testing of how CT-based AI should be annotated, validated, displayed, and governed. Methods: This focused narrative review combines evidence across the surgical workflow, spanning preoperative planning and risk stratification, intraoperative support, and postoperative monitoring. Reporting standards, implementation frameworks, governance, and regulatory sources were also considered when directly relevant to clinical deployment. Results: Across the available literature on breast reconstruction with the DIEP flap, preoperative CTA has been associated with reductions in operative time of approximately 54–76 min in individual studies. Semi-automated perforator mapping can reduce review time from 2 to 3 h to approximately 30 min. Intraoperative extended-reality tools and surgeon-facing navigation systems illustrate the importance of the ‘last mile’ of translation, while postoperative monitoring models show how imaging-linked data can support a closed-loop learning system. Across these stages, recurring limits include target mismatch, weak external validation, protocol variability, inconsistent reporting, limited subgroup analysis, and inadequate integration of economic and governance considerations. Conclusions: We argue that the next important step is not a generic autonomous model, but a clinically deployable DIEP-CTA-AI program. The practical blueprint proposed here is staged: structured anatomical labels, separate imaging, surgeons’ decisions, and outcome reference standards, dense intermediate endpoints, retrospective and external validation, reader studies, prospective silent deployment, and workflow-impact assessment. If implemented in this way, DIEP flap CTA can serve as a practical blueprint for CT-based AI translation in surgery more broadly.
1. Introduction
Artificial intelligence in surgery is expanding rapidly, but clinically credible deployment remains uneven. In a 2024 systematic review of 102 clinical surgical AI studies, Kenig et al. found high-evidence validation in only 45% of studies and public datasets in only 14% [1]. Broader 2025 reviews describe a sharp acceleration in publications and widening applications across all clinical phases, while also emphasizing persistent concerns regarding reproducibility, ethics, and implementation [2,3]. Malik et al. further noted that AI activity in surgery increased by more than 400% over the preceding five years, underscoring how quickly enthusiasm has outpaced translation [3]. The implementation gap is now being framed more explicitly as a lifecycle problem rather than a single-model problem. The 2025 JAMA Summit report argued that health AI should be developed, evaluated, regulated, disseminated, and monitored in an integrated fashion. The reason is that a tool’s effects depend not only on technical performance but also on human–computer interface, user training, and deployment setting [4]. In parallel, proposals for health AI assurance laboratories and recent ethics reviews have highlighted the need for ongoing evaluation, governance, fairness monitoring, and clear accountability, rather than relying on one-time pre-deployment testing alone [5,6]. Recent international expert consensus in bariatric surgery reached similar conclusions, emphasizing the promise of AI while warning against overreliance, inadequate ethical frameworks, and insufficient user education [7]. These issues are especially important in reconstructive microsurgery. Success in free-flap surgery depends on anatomy-specific decisions, uncommon but consequential complications, and tight alignment between preoperative imaging, intraoperative execution, and postoperative surveillance. At the same time, reconstructive microsurgery has become one of the most clinically interesting environments for surgical AI because the specific planning questions and the downstream consequences of those decisions are observable [8,9]. CT-based AI deserves separate consideration from generic ‘AI in surgery’ because CT provides something unusually valuable: a stable, three-dimensional anatomical representation that can be measured, segmented, rendered, and revisited post-surgery to draw further conclusions. In many workflows, CT is already part of routine decision-making. In microsurgical breast reconstruction, CTA is not only an image archive; it is a planning instrument used to identify deep inferior epigastric artery perforators, assess fascial exit and intramuscular course, estimate pedicle quality, and anticipate flap harvest difficulty [10,11,12,13,14]. The leap from CTA-based planning to CTA-based AI is therefore shorter than in workflows that rely mainly on photographs, free-text reports, or intraoperative judgment alone. Among reconstructive applications, DIEP flap breast reconstruction is particularly well suited to a translational CT-AI program. The relevant anatomy is structured enough to permit reproducible annotation, the operative target is discrete, surgeon decisions are actionable, and outcomes can be linked to the original scan. This makes DIEP flap CTA an ideal model system for a wider surgical AI agenda—not because it is simple, but because it is structured enough to make failure measurable and improvement actionable. The translational lessons from DIEP-CTA-AI—structured labels, staged validation, workflow integration, and outcome linkage—also generalize to other CT-based planning domains. These include hepato-pancreato-biliary resection, complex hernia repair, vascular surgery, and cardiothoracic intervention planning [15,16]. In contrast to prior reviews that mainly catalog applications, this manuscript aims to define the translational pathway required for clinically deployable CT-based surgical AI. Specifically, it synthesizes current evidence across the surgical workflow and uses DIEP flap CTA to articulate how such a process should be integrated into a publishable, deployable research program.
2. Literature Search Strategy and Scope
This manuscript is a focused narrative review without meta-analysis designed to inform translational research planning and manuscript development for the Special Issue on artificial intelligence in surgical procedures. PubMed/MEDLINE, journal websites, and citation chaining were searched through February–March 2026 (Table 1). Search concepts were iteratively combined around computed tomography, CT angiography, artificial intelligence, machine learning, deep learning, surgery, plastic surgery, microsurgery, breast reconstruction, DIEP flap, perforator mapping, augmented or mixed reality, free-flap monitoring, reporting standards, implementation, and governance. Boolean operators, AND, OR, NOT were utilized.
Inclusion Criteria
Articles were included when they were English-language peer-reviewed studies, systematic reviews, meta-analyses, translational imaging studies, clinically evaluated workflow tools, implementation or ethics papers, regulatory guidance, or reporting-guideline articles relevant to adult surgical patients, CT/CTA or CT-linked vascular imaging, AI/machine learning/deep learning, DIEP or free-flap reconstruction, perforator mapping, or surgical workflow implementation. Articles were excluded when they were non-English, animal-only or laboratory studies without translational relevance, abstracts without retrievable full text, duplicate publications, studies centered on non-CT modalities without a direct link to CTA-based planning, or AI papers without a clear planning, decision, or outcome link.
Studies on related but non-AI technologies, including augmented reality, virtual or mixed reality, projection guidance, and dedicated perforator-mapping software, were retained only when they used CT/CTA or vascular imaging to address the same translational problem: how preoperative anatomic information can become a surgeon-facing planning or guidance tool. These papers were therefore interpreted as evidence about display, registration, workflow integration, and human factors, rather than as evidence for algorithmic AI performance.
Preference was given to systematic reviews, meta-analyses, translational imaging studies, clinically evaluated workflow tools, implementation or ethics papers, regulatory sources, and reporting-guideline articles. The review was organized by workflow stage—preoperative planning, intraoperative support, and postoperative monitoring—with additional emphasis on failure modes, validation, economic evaluation, governance, and implementation requirements relevant to a real-world DIEP-CTA-AI program. Methodologically, the review was informed by current reporting and evaluation frameworks for AI in medical imaging and prediction modeling, including CLAIM, TRIPOD+AI, PROBAST+AI, DECIDE-AI, CONSORT-AI, SPIRIT-AI, and recent AI-specific reporting checklists [17,18,19,20,21,22,23].
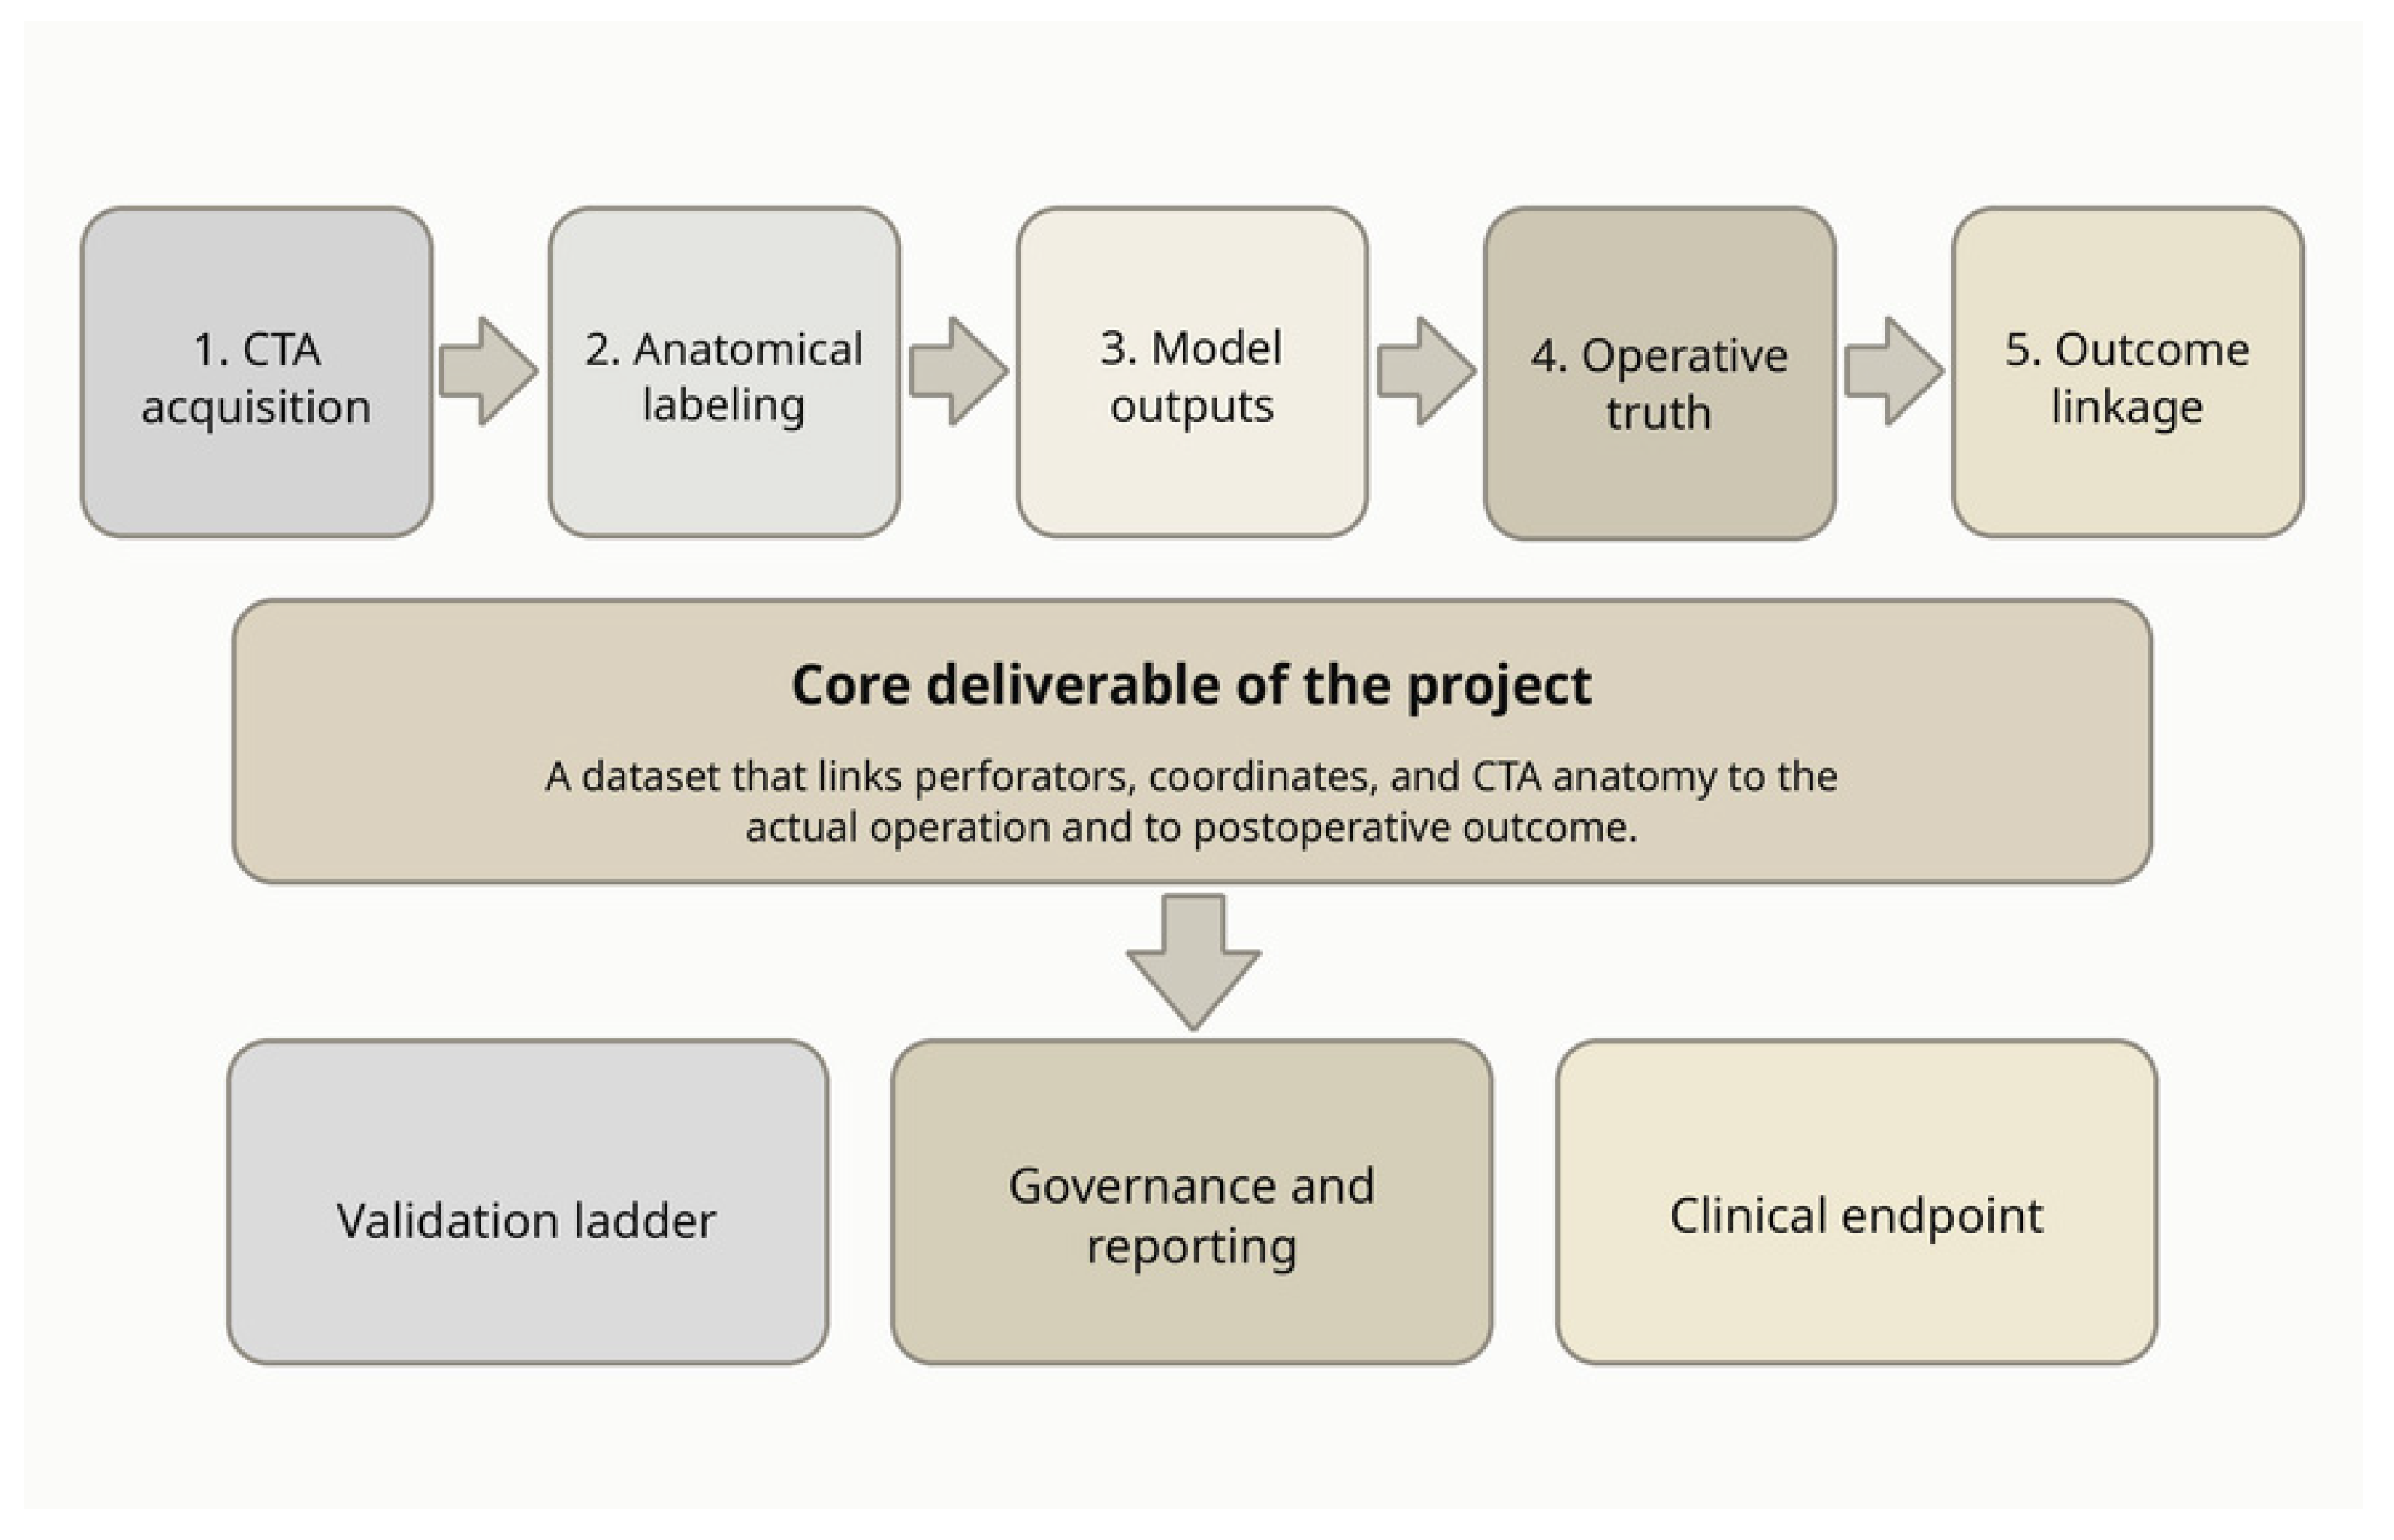
Because this manuscript was designed as a focused narrative review rather than a systematic review or meta-analysis, the selection process was recorded narratively rather than as a formal PRISMA flow diagram. After iterative searches and citation chaining, titles, abstracts, and available full texts were reviewed for relevance to CT-based surgical AI, reconstructive microsurgery, workflow translation, and governance. Sources were retained when they were directly useful for the purpose of this article or for defining the DIEP-CTA-AI translational pathway. A systematic review with meta-analysis was not attempted because the literature is highly heterogeneous across imaging protocols, anatomical targets, algorithm architectures, reference standards, clinical endpoints, and study objectives. More importantly, the objective of this article is not to estimate pooled effect sizes for a single narrowly defined intervention, but to define the translational pathway from development to deployment (Figure 1).
Figure 1.
Simplified translational pathway for a clinically deployable DIEP-CTA-AI program.
Table 1.
Representative evidence relevant to CT-based AI translation across the surgical workflow.
3. Why CT and CTA Are a Good Choice for Surgical AI: Benefits and Limitations
3.1. Benefits of CT/CTA for Surgical AI
Many surgical AI papers remain detached from the image modalities that drive operative decisions. CT is different. It is volumetric, reproducible, and inherently anatomical. It can represent vessel caliber, branching pattern, intramuscular course, fascial exit, spatial relation to stable landmarks, and relevant pathology within the same examination. Compared with ultrasound, which is operator-dependent and has a limited field of view, magnetic resonance imaging, which can be time-consuming and costly, or intraoperative Doppler, which is subjective and non-archivable, CTA offers retrospectively auditable three-dimensional data that can be shared across institutions and linked to generalizable models. DIEP flap CTA illustrates this advantage clearly. The planning task is not simply to ‘find vessels’, but to identify which perforators are likely to be surgically useful. This should enable the decision on the preferable hemiabdomen. Predictions on how difficult the harvest may be, whether the dominant perforator is in the medial or lateral row, how long the intramuscular dissection may be, and whether the anatomy is favorable for a time-efficient harvest should be feasible. Each of these questions can, at least in principle, be linked to structured labels on CTAs and traced forward to operational metrics and postoperative outcomes. A second advantage is workflow fit. The best surgical AI tool is not necessarily the most technically complex; it is the one that enters an existing workflow with minimal friction. CTA already sits upstream of radiology reporting, planning conferences, and operative selection in many microsurgical practices. An AI layer built on CTA therefore has a plausible path to routine use, provided it improves speed, agreement, or confidence without obscuring the surgeon’s own spatial reasoning.
3.2. Limitations of CT/CTA and Standardization Requirements
However, CTA is associated with several important limitations, such as ionizing radiation exposure, and the use of iodinated contrast agents carries a risk of adverse reactions, including allergic responses and contrast-induced nephropathy. CT imaging is also relatively costly compared to other modalities such as ultrasound, potentially limiting accessibility in resource-constrained settings.
The variability between scanners, acquisition protocols, dose settings, and reconstruction algorithms can affect image quality and quantitative measurements, posing challenges for standardization and reproducibility, particularly in multi-center studies and when developing imaging-based artificial intelligence applications.
For DIEP-CTA-AI, these issues should be built into the protocol from the beginning: scanner type, contrast timing, slice thickness, reconstruction kernel, image-quality flags, harmonization, and domain-adaptation strategies should be documented and planned rather than corrected only after external validation has failed.
4. Evidence by Surgical Workflow Stage
4.1. Preoperative Phase: Where CT-Based AI Is Currently Strongest
Any serious discussion of CTA-based AI should begin with the observation that CTA itself already improves preoperative planning. In an early clinical study, Uppal et al. reported that CT perforator mapping was associated with a mean reduction in operative time of 1 h and 16 min (approximately 21%), along with estimated hospital cost savings and fewer complications [10]. Wade et al. later showed in a systematic review and meta-analysis that preoperative perforator mapping by CTA or MRA reduced operating time by a mean of 54 min compared with no mapping, with CTA outperforming ultrasound and associated with lower partial flap failure [11]. More recently, Rupra et al. pooled 18 studies, 3870 patients, and 4283 flaps and concluded that CTA-guided planning is associated with lower partial and total flap loss, although the pooled reduction in operative time did not reach statistical significance due to substantial heterogeneity (I2 = 98.7%) [12]. These data matter because AI should not be framed as a replacement for a weak baseline. In DIEP reconstruction, the evidence-supported baseline is conventional CTA. The next step after conventional CTA is structured image analysis. In a clinically important study, Mavioso et al. showed that automatic perforator detection for microsurgical reconstruction could reduce preoperative analysis time by approximately 2 h per case compared to manual mapping, while still producing clinically useful localization and caliber information [14]. CTA can also standardize the learning curve. Ngaage et al. reported that the combination of CTA and venous couplers reduced operative and ischemia times in microvascular breast reconstruction, with the main contribution arising from CTA itself [13]. Their conclusion was pragmatic: CTA provides a vascular roadmap that mitigates early variability in flap planning and harvest. Taken together, the preoperative literature supports CTA as the current planning baseline and the most credible entry point for CT-based surgical AI. The design implications of this evidence are taken forward in the Section 5 below.
4.2. Intraoperative Phase: Translation Requires the Surgeon’s View
A preoperative model that never reaches the operating field has limited clinical value. Even when a CTA-based system performs well retrospectively, its clinical importance depends on whether the output can be displayed, interpreted, and acted upon under real constraints of clinical action. The ‘last mile’ of surgical AI—translating preoperative predictions into intraoperative action—meets unique barriers. Even highly accurate models fail if outputs cannot be displayed during surgery. A recent qualitative study of intraoperative AI implementation similarly found that barriers and facilitators extended well beyond algorithm accuracy to include workflow fit, trust, and contextual mismatch [32]. Early visualization studies in DIEP reconstruction are instructive. Lohasammakul et al. combined conventional CTA with Surgical Theater rendering for DIEP flap planning and reported high-fidelity three-dimensional visualization, a mean mapping time of 30.8 min, and intraoperative perforator identification and selection time of 36 min in a seven-patient series [24]. Importantly, one dominant perforator was identified intraoperatively despite not being apparent on CTA. Clinically, that observation matters because it confirms that surgeon judgment remains indispensable and that any AI-assisted system must preserve explicit human override rather than implying false certainty. Other groups have focused on direct projection or mixed-reality guidance. Meier et al. demonstrated the feasibility of projected augmented reality using dynamic infrared thermography in DIEP reconstruction and showed strong correlation between DIRT hotspots, handheld Doppler, and CTA data [25]. Necker et al. subsequently reported that the HoloDIEP mixed-reality tool was both faster and more accurate than Doppler-based intraoperative perforator mapping, with approximately half the localization error and roughly half the mapping time per abdomen [26]. Registration error remains a major limitation in surgical augmented reality, arising when preoperative images are misaligned with the intraoperative anatomy. This mismatch is particularly pronounced in soft tissues, which deform dynamically during surgery, and with even minor patient movement, both of which can invalidate rigid registration assumptions. As a result, spatial inaccuracies may compromise the reliability of AR guidance and limit its safe clinical integration. These studies are not all ‘AI’ in the narrowest sense, but they address the problem of how preoperative information becomes operative guidance, which AI alone does not solve.
4.3. Postoperative Phase: The Mature End of the AI Pathway
The strongest real-world deployment data in reconstructive microsurgery currently derives from postoperative monitoring rather than from preoperative CTA analysis. That observation is useful rather than disappointing. It shows what successful clinical AI looks like when the endpoint is practical, the sensor is easy to acquire, and the intervention pathway is clear. Huang et al. reported a supervised machine-learning model for postoperative free-flap monitoring in 805 flaps that achieved high overall accuracy and relied heavily on temperature and color differences as important features [27]. Kim et al. subsequently described an automated free-flap monitoring system using 11,112 photographs from 305 patients, with an AUC of 0.960 and prospective feasibility demonstrated in automated bedside sessions [28]. A 2025 systematic review and meta-analysis by Shekouhi et al. pooled 12 studies and reported a summary ROC AUC of 0.91, with pooled sensitivity of 78% and specificity of 88% [29]. These models are encouraging, but they also expose a gap. They often begin after the reconstructive plan has already been chosen. They can detect evolving compromise, but they do not explain whether a different perforator selection, flap design, or harvest strategy upstream might have reduced risk. For this reason, postoperative models should not be treated as substitutes for preoperative CTA-based decision support. They are better understood as the final stage of a closed-loop system in which preoperative anatomy, intraoperative decisions, and postoperative events are linked. A related lesson is that rare-event endpoints are poor starting targets. O’Neill et al. illustrated this problem in a machine-learning model for flap failure in microvascular breast reconstruction: development-set performance appeared strong, but test performance was substantially weaker, highlighting how quickly optimism can arise when event counts are low [30]. Similar caution has emerged in free-flap outcome prediction in head and neck reconstruction [31]. The appropriate conclusion is not that prediction is impossible, but that early translational projects should begin with dense, measurable, surgeon-relevant intermediate endpoints before advancing to rare complications.
5. Blueprint for a Clinically Deployable DIEP-CTA-AI Program
A useful DIEP-CTA-AI project should start from the end user backward. The end user is not the algorithm developer; it is the surgeon, radiologist, or multidisciplinary team member who must make a time-sensitive planning decision. The first deliverable should therefore be a structured planning aid rather than an autonomous recommendation. At minimum, the system should identify the perforator tree, estimate the fascial exit coordinates, measure caliber, characterize the intramuscular course, and produce a ranked shortlist of candidate perforators, with the uncertainty explicitly quantified. The dataset must support that task across four linked levels: imaging, anatomy, clinical decisions, and outcomes (Table 2).
Table 2.
Proposed four-level dataset structure for a clinically deployable DIEP-CTA-AI program.
Without these linked labels, the project will remain a segmentation exercise rather than a clinical decision-support platform. The earliest primary endpoints should be chosen for density and clinical relevance. Suitable first targets include millimeter error in fascial exit localization, sensitivity for clinically relevant perforators above a predefined caliber threshold, top-1 and top-3 agreement with surgeon-selected perforators, reduction in structured-report time, and improvement in reader-study confidence or inter-rater agreement. These targets are preferable to the immediate prediction of rare events such as flap loss. Once those endpoints are achieved, the validation ladder should progress from internal testing to a temporal holdout, external-center validation, surgeon or radiologist reader studies, prospective silent deployment, and, finally, workflow-impact evaluation. This order separates model performance from workflow effect and reduces the risk of overclaiming based on rare complications.
A credible DIEP-CTA-AI program requires a multi-year and ideally multicenter commitment rather than a single retrospective manuscript. A realistic roadmap is as follows: Phase 1 should focus on dataset assembly, development of the annotation protocol, IRB approval, and pilot annotation, with an initial target of approximately 100–150 fully linked cases. Phase 2 should expand annotation, support model development and internal validation, and prepare a formal reader study, ideally reaching 300–500 cases from multiple centers with reliable operative linkage. Phase 3 should prioritize temporal holdout testing, external validation where available, and prospective silent deployment within the clinical workflow. Phase 4 should be reserved for interventional study design, economic evaluation, regulatory planning, and post-deployment monitoring. This timeline assumes dedicated research coordinator support, protected annotation time from surgeons and imaging experts, and computational infrastructure capable of sustaining versioned model development and auditability. Annotation burden is a critical bottleneck and should be budgeted explicitly. In practical terms, a fully linked DIEP-CTA case may require roughly 30–60 min of expert time when anatomical labels, decision labels, operative linkage, and quality control are all captured. For a 300-case dataset, that corresponds to approximately 150–300 h of senior surgical and imaging labor. Mitigation measures include semi-automated pre-annotation, hierarchical workflows in which junior annotators prepare anatomy labels for senior review, and explicit academic credit or protected time for annotators.
Governance should be designed from the start rather than appended at submission. Cases with prior abdominal surgery, poor contrast timing, variant anatomy, uncertain labels, or postoperative rescue events should not be hidden; they should be explicitly tagged because they are precisely where clinical systems are likely to fail. Annotation provenance, uncertainty scores, dataset splits, scanner protocol, reconstruction parameters, and missingness should be recorded reproducibly. The project should also prespecify image harmonization or domain-adaptation approaches and subgroup analyses where available— BMI, prior surgery, and radiation history—because the deployment target is not a homogeneous benchmark set but a real patient population [6,20,33]. For workflow deployment, the core unit of innovation is not just the algorithm; it is the complete human-in-the-loop system. The intended use should state that the tool supports surgeon decision-making rather than replacing it, and the clinical record should document the AI output, surgeon acceptance or override, and the rationale for final perforator selection. Economic evaluation is likewise essential for adoption. A DIEP-CTA-AI system that reduces review time and unnecessary intraoperative exploration has obvious value, but implementation costs—including software development, infrastructure, annotation labor, maintenance, and governance—must be weighed against these gains [14,34]. For that reason, cost-effectiveness should be treated as a planned work package rather than a post hoc argument.
6. Discussion
The literature suggests that CT-based AI in surgery is most promising when it is anchored to existing planning workflows rather than inserted as an abstract diagnostic layer. DIEP flap CTA fits that requirement unusually well. CTA already reduces uncertainty and operative time [10,11,12,13]. Semi-automated perforator analysis shows that image interpretation can be accelerated without discarding clinically useful detail [14]. Extended-reality tools show how image-derived planning can be translated into the surgeon’s workspace [24,25,26]. Postoperative monitoring models show what a more mature clinical AI pathway looks like when evaluation progresses beyond retrospective accuracy [27,28,29]. The challenge now is to connect these items rather than treating them as separate innovations. This manuscript is intentionally positioned as a translational framework rather than a validation study. Its main contribution is conceptual and programmatic: it argues that the first strong DIEP-CTA-AI paper should benchmark anatomically faithful model outputs versus operative truth. Datasets must separate imaging, decision, and outcome reference standards, and deployment requires a staged ladder extending from retrospective development to reader studies, silent clinical use, and workflow-impact evaluation. In that sense, the review attempts to prepare a research program, not just summarize a field. The focus on DIEP flap CTA should not be misread as a limitation of relevance. Rather, it provides a base structure for the results whose lessons are likely to generalize to other CT-centered planning domains such as hepato-pancreato-biliary surgery, cardiothoracic intervention planning, vascular surgery, and selected abdominal wall or hernia workflows. Recent systematic and narrative reviews in HPB and cardiothoracic surgery describe a similar pattern: good technical feasibility, strong reliance on high-quality imaging, and persistent barriers in external validation, workflow integration, and prospective evaluation [15,16].
If a translational framework cannot survive in the relatively well-structured environment of DIEP-CTA, it is unlikely to fare better in less structured domains. Responsible implementation also calls for attention to economics, bias, and lifecycle monitoring. Health-system stakeholders will ask whether a planning tool saves time, reduces variability, avoids unnecessary dissection, or improves downstream outcomes enough to justify its cost [4,34]. They will also ask whether the tool behaves consistently across patient subgroups and scanner protocols, and whether its performance drifts over time. The policy literature increasingly treats these as core requirements rather than optional extras, which is why lifecycle evaluation, assurance infrastructure, and post-deployment monitoring are becoming central to health AI governance [4,5,6]. Evidence from medical imaging more broadly shows that models can encode demographic shortcuts and appear fair in-distribution while degrading in new settings [33]. Surgeons must also guard against automation bias, ensuring that AI supports rather than displaces professional judgment and patient trust [6].
Regulatory pathways for CT-based surgical AI remain evolving, but they cannot be treated as an afterthought. In both the United States and Europe, AI-enabled device software is increasingly being framed around intended use, lifecycle documentation, change management, and post-deployment monitoring rather than one-off retrospective accuracy claims [35,36]. Early engagement with regulatory, procurement, and institutional governance stakeholders should therefore begin during dataset and workflow design, not after model development is complete. Equally important is the publication strategy. The review presented here can function as the conceptual anchor. The natural first empirical companion study is a linked retrospective dataset and a validation paper that benchmarks anatomical outputs against operative truth.
An additional translational challenge is that strong development performance does not necessarily indicate clinically reliable model behavior. It is important to recognize that overfitting may produce deceptively high retrospective accuracy while masking poor real-world generalizability. Learning curves comparing training and validation performance are therefore valuable diagnostic tools. A widening gap in which training accuracy continues to improve while validation performance plateaus or deteriorates may indicate that the model is memorizing center-specific or dataset-specific imaging patterns rather than learning anatomically meaningful relationships. This problem is particularly relevant in CT-based surgical AI because datasets are often modest in size and vulnerable to hidden correlations related to scanner type, reconstruction kernel, or institutional workflow. Similarly, data leakage remains a major but underrecognized source of inflated performance; this can occur if scans are inadvertently reused across dataset splits, or if postoperative information becomes unintentionally encoded into training labels. For this reason, strict patient-level separation, temporal holdout testing, and external-center validation should be treated as fundamental design requirements rather than optional refinements.
Evaluation metrics also require careful interpretation, especially in reconstructive microsurgery where clinically important adverse events such as flap compromise, take-back, or total flap loss are relatively uncommon. In these imbalanced datasets, conventional accuracy may appear artificially high simply because most cases belong to the uncomplicated majority class. Precision–recall curves are therefore often more informative than accuracy alone because they better characterize model behavior on rare but clinically consequential outcomes. Calibration analyses, subgroup testing, and prospective reader studies are similarly important because a technically accurate model may still fail if predictions are poorly calibrated or inconsistent across acquisition environments. Several methodological safeguards can reduce these risks. Regularization techniques such as dropout, weight decay, data augmentation, and early stopping may improve generalizability by discouraging memorization of noise or institution-specific imaging artifacts. Harmonization strategies across scanners and acquisition protocols are equally important for improving transportability in multicenter deployment. Together, these considerations reinforce a central argument of this review: clinically deployable DIEP-CTA-AI depends not only on sophisticated algorithms, but also on rigorous training methodology, transparent validation practices, and careful integration into real-world surgical workflows.
Limitations
This is a focused narrative review without meta-analysis rather than a formal systematic review and therefore does not claim exhaustive coverage of every relevant article or pooled estimation of a single intervention effect. The focus on DIEP flap CTA narrows the clinical lens, although we argue that this specificity is a strength for translational design because it forces attention to concrete labels, decisions, and outcomes. The proposed blueprint has not itself been prospectively tested; future research must determine whether following this pathway actually improves planning quality, process efficiency, cost-effectiveness, or clinical outcomes.
Another limitation is that CT/CTA is not the same examination at every center. Differences in scanner hardware, dose settings, contrast timing, slice thickness, reconstruction algorithms, and post-processing can change vessel conspicuity and quantitative measurements. These differences may reduce model transportability and may produce site-specific failure modes if they are not considered at the design stage. Future DIEP-CTA-AI studies should therefore prespecify protocol documentation, image-quality thresholds, harmonization procedures, domain-adaptation strategies, and external validation across acquisition environments.
Finally, regulatory clearance pathways, reimbursement strategies, and detailed medico-legal questions were not examined comprehensively here, even though they will matter for real-world deployment. A system that influences perforator selection or flap-harvest planning may affect operative choices and, in the event of adverse outcomes, raises questions about responsibility allocation among the surgeon, radiologist, institution, and software developer. Prospective deployment should therefore define the intended use, document whether the AI output was accepted or overridden, record the surgeon’s rationale in the clinical record, preserve an audit trail of model version and input data, and establish escalation pathways for uncertain or discordant recommendations.
7. Conclusions
CT-based artificial intelligence across the surgical workflow is best understood not as a single model, but as a linked system spanning planning, execution, and follow-up. In reconstructive microsurgery, DIEP flap CTA offers one of the clearest opportunities to build such a system because anatomy, surgeon decisions, and outcomes can all be structured and connected. If built in that way, the project would do more than automate perforator mapping. It would provide a realistic template for how CT-based AI can move from image analysis to trustworthy surgical decision support. As surgical AI moves from proof-of-concept to clinical deployment, the field’s credibility will depend on whether early translational programs demonstrate not only technical feasibility, but measurable improvements in the clinical setting.
Author Contributions
Conceptualization, C.E.R.K. and V.F.M.H.; methodology, C.E.R.K.; validation, C.E.R.K., N.W., G.H., J.-F.H. and V.F.M.H.; investigation, C.E.R.K.; resources, V.F.M.H.; data curation, C.E.R.K., J.-F.H. and V.F.M.H.; writing—original draft preparation, C.E.R.K.; writing—review and editing, C.E.R.K., N.W., G.H., J.-F.H. and V.F.M.H.; visualization, C.E.R.K., N.W., G.H., J.-F.H. and V.F.M.H.; supervision, V.F.M.H.; project administration, C.E.R.K. and V.F.M.H.; All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Kenig, N.; Monton Echeverria, J.; Muntaner Vives, A. Artificial Intelligence in Surgery: A Systematic Review of Use and Validation. J. Clin. Med. 2024, 13, 7108. [Google Scholar] [CrossRef] [Scilit]
- Chevalier, O.; Dubey, G.; Benkabbou, A.; Majbar, M.A.; Souadka, A. Comprehensive Overview of Artificial Intelligence in Surgery: A Systematic Review and Perspectives. Pflug. Arch. 2025, 477, 617–626. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malik, A.P.; Ahmad, W.; Iqbal, J. The AI Surge in Surgery: Evolution, Challenges, and Ethical Considerations. Ann. BioMed Eng. 2025, 53, 1989–1992. [Google Scholar] [CrossRef] [Scilit]
- Angus, D.C.; Khera, R.; Lieu, T.; El Naqa, I.; Atun, R.; Banerjee, I.; Beg, M.S.; Chute, C.G.; Collins, F.S.; Cummings, S.R.; et al. AI, Health, and Health Care Today and Tomorrow: The JAMA Summit Report on Artificial Intelligence. JAMA 2025, 334, 1650–1664. [Google Scholar] [CrossRef] [Scilit]
- Shah, N.H.; Halamka, J.D.; Saria, S.; Pencina, M.J.; Tazbaz, T.; Barker, W.; Bell, D.S.; Bhatia, N.; Brat, G.A.; Cohen, I.G.; et al. A Nationwide Network of Health AI Assurance Laboratories. JAMA 2024, 331, 245–249. [Google Scholar] [CrossRef] [Scilit]
- Yu, E.; Rosenberg, G.M.; Udelsman, B.V.; Juo, Y.Y.; Mak, K.S.; Chang, G.J.; Tsung, A.; Pawlik, T.M. Narrative Review of the Ethics of Artificial Intelligence: Are We Ready for Artificial Intelligence in Surgery? J. Thorac. Dis. 2026, 18, 173. [Google Scholar] [CrossRef] [Scilit]
- Kermansaravi, M.; Chiappetta, S.; Shahabi Shahmiri, S.; Gagner, M.; Brethauer, S.A.; Schauer, P.R.; Iannelli, A.; Cottam, D.; Keshishian, A.; Lakdawala, M.; et al. International Expert Consensus on the Current Status and Future Prospects of Artificial Intelligence in Metabolic and Bariatric Surgery. Sci. Rep. 2025, 15, 9312. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shadid, O.; Seth, I.; Cuomo, R.; Rozen, W.M.; Marcaccini, G. Artificial Intelligence in Microsurgical Planning: A Five-Year Leap in Clinical Translation. J. Clin. Med. 2025, 14, 4574. [Google Scholar] [CrossRef] [Scilit]
- Rugina, A.I.; Ungureanu, A.; Giuglea, C.; Marinescu, S.A. Artificial Intelligence in Breast Reconstruction: A Narrative Review. Medicina 2025, 61, 440. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Uppal, R.S.; Casaer, B.; Van Landuyt, K.; Blondeel, P.N.; Hamdi, M.; Vermeersch, H.; Monstrey, S. The Efficacy of Preoperative Mapping of Perforators in Reducing Operative Times and Complications in Perforator Flap Breast Reconstruction. J. Plast. Reconstr. Aesthet. Surg. 2009, 62, 859–864. [Google Scholar] [CrossRef] [Scilit]
- Wade, R.G.; Watford, J.; Wormald, J.C.R.; Bramhall, R.J.; Figus, A. Perforator Mapping Reduces the Operative Time of DIEP Flap Breast Reconstruction: A Systematic Review and Meta-analysis of Preoperative Ultrasound, Computed Tomography and Magnetic Resonance Angiography. J. Plast. Reconstr. Aesthet. Surg. 2018, 71, 468–477. [Google Scholar] [CrossRef] [Scilit]
- Rupra, R.S.; Ruccia, F.; Daneshi, K.; Jallali, N.; Whitaker, I.S.; Jallali, N.; Ramakrishnan, V.V. A Systematic Review and Meta-analysis on Computed Tomography Angiography Mapping for Deep Inferior Epigastric Perforator Flap Breast Reconstruction. Front. Oncol. 2025, 15, 1600476. [Google Scholar] [CrossRef] [Scilit]
- Ngaage, L.M.; Oni, G.; Di Pace, B.; Boyce, M.; Cheong, E.; Ramakrishnan, V. The Effect of CT Angiography and Venous Couplers on Surgery Duration in Microvascular Breast Reconstruction: A Single Operator’s Experience. Gland Surg. 2018, 7, 440–448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mavioso, C.; Araujo, R.J.; Oliveira, H.P. Automatic Detection of Perforators for Microsurgical Reconstruction. Breast 2020, 50, 19–24. [Google Scholar] [CrossRef] [Scilit]
- Mank, Q.J.; Thabit, A.; Maat, A.P.W.M.; van den Heuvel, A.F.M.; Bouwman, R.A.; Maessen, J.G.; van Putte, B.P.; de Kroon, T.L.; de Mol, B.A.J.M.; de Jaegere, P.P.T.; et al. State-of-the-art Artificial Intelligence Methods for Pre-operative Planning of Cardiothoracic Surgery and Interventions: A Narrative Review. J. Thorac. Dis. 2025, 17, 5282–5297. [Google Scholar] [CrossRef] [Scilit]
- Efstathiou, A.; Charitaki, E.; Triantopoulou, C.; Delis, S. Artificial Intelligence and Digital Tools Across the Hepato-Pancreato-Biliary Surgical Pathway: A Systematic Review. J. Clin. Med. 2025, 14, 6501. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tejani, A.S.; Klontzas, M.E.; Gatti, A.A.; Rubin, D.L.; Kalpathy-Cramer, J.; Lungren, M.P.; Kohli, M.D.; Dreyer, K.J.; Prevedello, L.M.; Allen, B.; et al. Checklist for Artificial Intelligence in Medical Imaging (CLAIM): 2024 Update. Radiol. Artif. Intell. 2024, 6, e240300. [Google Scholar] [CrossRef] [Scilit]
- Collins, G.S.; Dhiman, P.; Andaur Navarro, C.L.; Ma, J.; Hooft, L.; Reitsma, J.B.; Logullo, P.; Beam, A.L.; Peng, L.; Van Calster, B.; et al. TRIPOD+AI Statement: Updated Guidance for Reporting Clinical Prediction Models That Use Regression or Machine Learning Methods. BMJ 2024, 385, e078378. [Google Scholar] [CrossRef] [Scilit]
- Moons, K.G.M.; Andaur Navarro, C.L.; Beam, A.L.; Damen, J.A.A.G.; Debray, T.P.A.; Dhiman, P.; Hooft, L.; Riley, R.D.; Reitsma, J.B.; Wynants, L.; et al. PROBAST+AI: An Updated Quality, Risk of Bias, and Applicability Assessment Tool for Prediction Models Using Regression or Artificial Intelligence Methods. BMJ 2025, 388, e082505. [Google Scholar] [CrossRef] [Scilit]
- Vasey, B.; Nagendran, M.; Campbell, B.; Clifton, D.A.; Collins, G.S.; Denaxas, S.; Denniston, A.K.; Faes, L.; Geerts, B.; Ibrahim, M.; et al. Reporting Guideline for the Early Stage Clinical Evaluation of Decision Support Systems Driven by Artificial Intelligence: DECIDE-AI. BMJ 2022, 377, e070904. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, X.; Cruz Rivera, S.; Moher, D.; Calvert, M.J.; Denniston, A.K. SPIRIT-AI and CONSORT-AI Working Group. Reporting Guidelines for Clinical Trial Reports for Interventions Involving Artificial Intelligence: The CONSORT-AI Extension. BMJ 2020, 370, m3164. [Google Scholar] [CrossRef] [Scilit]
- Cruz Rivera, S.; Liu, X.; Chan, A.W.; Denniston, A.K.; Calvert, M.J. SPIRIT-AI and CONSORT-AI Working Group. Guidelines for Clinical Trial Protocols for Interventions Involving Artificial Intelligence: The SPIRIT-AI Extension. BMJ 2020, 370, m3210. [Google Scholar] [CrossRef] [Scilit]
- Kwak, S.G.; Kim, J. Comprehensive Reporting Guidelines and Checklist for Studies Developing and Utilizing Artificial Intelligence Models. Korean J. Anesthesiol. 2025, 78, 199–214. [Google Scholar] [CrossRef] [Scilit]
- Lohasammakul, S.; Flor, M.; Hoye, C.; Selber, J.C. Surgical Theater, a Novel Technology, Enhances 3-dimensional Mapping for Robotic-assisted Deep Inferior Epigastric Perforator Free Flap. Plast. Reconstr. Surg. Glob. Open 2025, 13, e6872. [Google Scholar] [CrossRef] [Scilit]
- Meier, E.L.; Ulrich, D.J.O.; Hummelink, S. Projected Augmented Reality in DIEP Flap Breast Reconstruction: Projecting Perforators on the Skin Using Dynamic Infrared Thermography. J. Plast. Reconstr. Aesthet. Surg. 2024, 94, 83–90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Necker, F.N.; Cholok, D.J.; Fischer, M.J.; Kurlander, D.E.; Sacks, J.M. HoloDIEP—Faster and More Accurate Intraoperative DIEA Perforator Mapping Using a Novel Mixed Reality Tool. J. Reconstr. Microsurg. 2025, 41, 318–329. [Google Scholar] [CrossRef] [Scilit]
- Huang, R.W.; Tsai, T.Y.; Hsieh, Y.H.; Lin, C.H.; Lin, Y.T.; Kao, H.K. Reliability of Postoperative Free Flap Monitoring with a Novel Prediction Model Based on Supervised Machine Learning. Plast. Reconstr. Surg. 2023, 152, 943e–952e. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.; Lee, S.M.; Kim, D.E.; Lee, T.J.; Jeong, W.S.; Rah, D.K.; Hong, J.P. Development of an Automated Free Flap Monitoring System Based on Artificial Intelligence. JAMA Netw. Open 2024, 7, e2424299. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shekouhi, R.; Darabi, H.; Chim, H. Diagnostic Accuracy of Artificial Intelligence Models for Predicting Postoperative Complications Following Free Flap Reconstruction: A Systematic Review and Meta-analysis. Microsurgery 2025, 45, e70143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Neill, A.C.; Yang, D.; Roy, M.; Sebastiampillai, S.; Hofer, S.O.P.; Xu, W. Development and Evaluation of a Machine Learning Prediction Model for Flap Failure in Microvascular Breast Reconstruction. Ann. Surg. Oncol. 2020, 27, 3466–3475. [Google Scholar] [CrossRef] [Scilit]
- Asaad, M.; Lu, S.C.; Hassan, A.M.; Kambhampati, P.; Mitchell, D.; Chang, E.I.; Yu, P.; Hanasono, M.M.; Sidey-Gibbons, C. The Use of Machine Learning for Predicting Complications of Free-flap Head and Neck Reconstruction. Ann. Surg. Oncol. 2023, 30, 2343–2352. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Thornton, M.; Cher, B.A.Y.; Macdonald, C.; Baker, J.G.; Marten, E.L.; Mai, D.; Sankaranarayanan, G.; Balentine, M.D. Expectations vs. Reality of an Intraoperative Artificial Intelligence Intervention. JAMA Surg. 2026, 161, 234–240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, Y.; Zhang, H.; Gichoya, J.W.; Katabi, D.; Ghassemi, M. The Limits of Fair Medical Imaging AI in Real-world Generalization. Nat. Med. 2024, 30, 2838–2848. [Google Scholar] [CrossRef] [Scilit]
- El Arab, R.A.; Al Moosa, O.A. Systematic Review of Cost Effectiveness and Budget Impact of Artificial Intelligence in Healthcare. npj Digit. Med. 2025, 8, 548. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- U.S. Food and Drug Administration. Artificial Intelligence-Enabled Device Software Functions: Lifecycle Management and Marketing Submission Recommendations. 2025. Available online: https://www.fda.gov/regulatory-information/search-fda-guidance-documents/artificial-intelligence-enabled-device-software-functions-lifecycle-management-and-marketing (accessed on 15 March 2026).
- European Union. Regulation (EU) 2024/1689 of the European Parliament and of the Council of 13 June 2024 Laying Down Harmonised Rules on Artificial Intelligence (Artificial Intelligence Act). Off. J. Eur. Union. 2024. Available online: https://eur-lex.europa.eu/eli/reg/2024/1689/oj/eng (accessed on 15 March 2026).

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.