Pediatric Electrocardiogram in Preparticipation Screening: Narrative Review of Normal Values in Key Features


Highlights
- Published pediatric ECG normal values show substantial variability, particularly for parameters related to left ventricular hypertrophy, QTc prolongation and pre-excitation, despite consistent age-related trends.
- Greater standardization of ECG acquisition and measurement methods, alongside age-specific interpretation, is needed to improve reliability of pediatric ECG screening.
Abstract
1. Introduction
2. Materials and Methods
2.1. Study Design
2.2. Search Strategy and Sources
2.3. Eligibility Criteria
2.4. Data Extraction and Synthesis
3. Results
3.1. Included Studies
3.2. LVH Criteria
3.3. Pre-Excitation Detection in Pediatric ECG
3.4. LQT Detection in Pediatric ECG
4. Discussion
5. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
Abbreviations
| ECG | Electrocardiography |
| LVH | Left Ventricular Hypertrophy |
| LQT | Long QT syndrome |
| WPW | Wolff–Parkinson–White Syndrome |
| mV | millivolts |
| ms | milliseconds |
References
- Maron, B.J.; Thompson, P.D.; Puffer, J.C.; McGrew, C.A.; Strong, W.B.; Douglas, P.S.; Clark, L.T.; Mitten, M.J.; Crawford, M.H.; Atkins, D.L.; et al. Cardiovascular preparticipation screening of competitive athletes: A statement for health professionals from the Sudden Death Committee (clinical cardiology) and Congenital Cardiac Defects Committee (cardiovascular disease in the young), American Heart Association. Circulation 1996, 94, 850–856. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pelliccia, A.; Di Paolo, F.M.; Corrado, D.; Buccolieri, C.; Quattrini, F.M.; Pisicchio, C.; Spataro, A.; Biffi, A.; Granata, M.; Maron, B.J. Evidence for efficacy of the Italian national pre-participation screening programme for identification of hypertrophic cardiomyopathy in competitive athletes. Eur. Heart J. 2006, 27, 2196–2200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Corrado, D.; Pelliccia, A.; Bjørnstad, H.H.; Vanhees, L.; Biffi, A.; Borjesson, M.; Panhuyzen-Goedkoop, N.; Deligiannis, A.; Solberg, E.; Dugmore, D.; et al. Cardiovascular pre-participation screening of young competitive athletes for prevention of sudden death: Proposal for a common European protocol: Consensus Statement of the Study Group of Sport Cardiology of the Working Group of Cardiac Rehabilitation and Exercise Physiology and the Working Group of Myocardial and Pericardial Diseases of the European Society of Cardiology. Eur. Heart J. 2005, 26, 516–524. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gregg, R.E.; Zhou, S.H.; Dubin, A.M. Automated detection of ventricular pre-excitation in pediatric 12-lead ECG. J. Electrocardiol. 2016, 49, 37–41. [Google Scholar] [CrossRef] [Scilit]
- Saarel, E.V.; Granger, S.; Kaltman, J.R.; Minich, L.L.; Tristani-Firouzi, M.; Kim, J.J.; Ash, K.; Tsao, S.S.; Berul, C.I.; Stephenson, E.A.; et al. Electrocardiograms in Healthy North American Children in the Digital Age. Circ. Arrhythmia Electrophysiol. 2018, 11, e005808. [Google Scholar] [CrossRef] [Scilit]
- Rijnbeek, P.R.; Witsenburg, M.; Schrama, E.; Hess, J.; Kors, J.A. New normal limits for the paediatric electrocardiogram. Eur. Heart J. 2001, 22, 702–711. [Google Scholar] [CrossRef] [Scilit]
- Bratincsák, A.; Kimata, C.; Limm-Chan, B.N.; Vincent, K.P.; Williams, M.R.; Perry, J.C. Electrocardiogram Standards for Children and Young Adults Using Z-Scores. Circ. Arrhythmia Electrophysiol. 2020, 13, e008253. [Google Scholar] [CrossRef] [Scilit]
- Woroniecki, R.P.; Kahnauth, A.; Panesar, L.E.; Supe-Markovina, K. Left Ventricular Hypertrophy in Pediatric Hypertension: A Mini Review. Front. Pediatr. 2017, 5, 101. [Google Scholar] [CrossRef] [Scilit]
- Tague, L.; Wiggs, J.; Li, Q.; McCarter, R.; Sherwin, E.; Weinberg, J.; Sable, C. Comparison of Left Ventricular Hypertrophy by Electrocardiography and Echocardiography in Children Using Analytics Tool. Pediatr. Cardiol. 2018, 39, 1378–1388. [Google Scholar] [CrossRef] [Scilit]
- Moore, G.P.; Munter, D.W. Wolff-Parkinson-White syndrome: Illustrative case and brief review. J. Emerg. Med. 1989, 7, 47–54. [Google Scholar] [CrossRef] [Scilit]
- Centurión, O.A.; Shimizu, A.; Isomoto, S.; Konoe, A. Mechanisms for the genesis of paroxysmal atrial fibrillation in the Wolff Parkinson-White syndrome: Intrinsic atrial muscle vulnerability vs. electrophysiological properties of the accessory pathway. Europace 2008, 10, 294–302. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Katyal, A.; Li, C.O.Y.; Franciosi, S.; Sanatani, S. The safety of sports in children with inherited arrhythmia substrates. Front. Pediatr. 2023, 11, 1151286. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Galić, E.; Bešlić, P.; Kilić, P.; Planinić, Z.; Pašalić, A.; Galić, I.; Ćubela, V.-V.; Pekić, P. Congenital Long QT Syndrome: A Systematic Review. Acta Clin. Croat. 2021, 60, 739–748. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davignon, A.; Rautaharju, P.; Boisselle, E.; Soumis, F.; Mégélas, M.; Choquette, A. Normal ECG standards for infants and children. Pediatr. Cardiol. 1980, 1, 123–131. [Google Scholar] [CrossRef] [Scilit]
- Dickinson, D.F. The normal ECG in childhood and adolescence. Heart 2005, 91, 1626–1630. [Google Scholar] [CrossRef] [Scilit]
- Andršová, I.; Hnatkova, K.; Helánová, K.; Šišáková, M.; Novotný, T.; Kala, P.; Malik, M. Problems with Bazett QTc correction in paediatric screening of prolonged QTc interval. BMC Pediatr. 2020, 20, 558. [Google Scholar] [CrossRef] [Scilit]
- Lue, H.-C.; Wu, M.-H.; Wang, J.-K.; Lin, M.-T.; Lu, C.-W.; Chiu, S.-N.; Chen, C.-A.; Wu, E.-T.; Wang, C.-C.; Fu, C.-M.; et al. Normal ECG standards and percentile charts for infants, children and adolescents. Pediatr. Neonatol. 2023, 64, 256–273. [Google Scholar] [CrossRef] [Scilit]
- Macfarlane, P.W.; Coleman, E.N.; Pomphrey, E.O.; McLaughlin, S.; Houston, A.; Aitchison, T. Normal limits of the high-fidelity pediatric ECG. Preliminary observations. J. Electrocardiol. 1989, 22, 162–168. [Google Scholar] [CrossRef] [Scilit]
- Semizel, E.; Oztürk, B.; Bostan, O.M.; Cil, E.; Ediz, B. The effect of age and gender on the electrocardiogram in children. Cardiol. Young 2008, 18, 26–40. [Google Scholar] [CrossRef] [Scilit]
- Kamphuis, V.P.; Blom, N.A.; van Zwet, E.W.; Man, S.; Ten Harkel, A.D.J.; Maan, A.C.; Swenne, C.A. Normal values of the ventricular gradient and QRS-T angle, derived from the pediatric electrocardiogram. J. Electrocardiol. 2018, 51, 490–495. [Google Scholar] [CrossRef] [Scilit]
- Yoshinaga, M.; Iwamoto, M.; Horigome, H.; Sumitomo, N.; Ushinohama, H.; Izumida, N.; Tauchi, N.; Yoneyama, T.; Abe, K.; Nagashima, M. Standard Values and Characteristics of Electrocardiographic Findings in Children and Adolescents. Circ. J. 2018, 82, 831–839. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Uygur, Ö.; Aydoğdu, A. Normal electrocardiogram values of healthy children. Turk. Pediatri Ars. 2019, 54, 93–104. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Landon, G.; Denjoy, I.; Clero, E.; Silenok, A.; Kurnosova, I.; Butsenin, A.; Gourmelon, P.; Jourdain, J.-R. Reference values of electrographic and cardiac ultrasound parameters in Russian healthy children and adolescents. Sci. Rep. 2021, 11, 2916. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pietrzak, R.; Gąsior, J.S.; Książczyk, T.; Tomik, A.; Werner, B. Electrocardiograms in school-aged healthy Polish children—An observational study. Kardiol. Pol. 2022, 80, 1211–1216. [Google Scholar] [CrossRef] [Scilit]
- Brockmeier, K.; Nazal, R.; Sreeram, N. The electrocardiogram of the neonate and infant. J. Electrocardiol. 2016, 49, 814–816. [Google Scholar] [CrossRef] [Scilit]
- Joyce, J.J.; Qi, N.; Chang, R.-K.; Ferns, S.J.; Baylen, B.G. Right and Left Ventricular Mass Development in Early Infancy: Correlation of Electrocardiographic Changes with Echocardiographic Measurements. J. Electrocardiol. 2023, 81, 101–105. [Google Scholar] [CrossRef] [Scilit]
- Harteveld, L.M.; Nederend, I.; Ten Harkel, A.D.J.; Schutte, N.M.; de Rooij, S.R.; Vrijkotte, T.G.M.; Oldenhof, H.; Popma, A.; Jansen, L.M.C.; Suurland, J.; et al. Maturation of the Cardiac Autonomic Nervous System Activity in Children and Adolescents. J. Am. Heart Assoc. 2021, 10, e017405. [Google Scholar] [CrossRef] [Scilit]
- Chan, T.C.; Sharieff, G.Q.; Brady, W.J. Electrocardiographic manifestations: Pediatric ECG. J. Emerg. Med. 2008, 35, 421–430. [Google Scholar] [CrossRef] [Scilit]
- Kittnar, O. Sex Related Differences in Electrocardiography. Physiol. Res. 2023, 72, S127–S135. [Google Scholar] [CrossRef] [Scilit]
- Carbone, V.; Guarnaccia, F.; Carbone, G.; Zito, G.B.; Oliviero, U.; Soreca, S.; Carbone, F. Gender differences in the 12-lead electrocardiogram: Clinical implications and prospects. J. Sex- Gend.-Specif. Med. 2020, 6, 126–141. [Google Scholar]
- De Bie, J.; Diemberger, I.; Mason, J.W. Comparison of PR, QRS, and QT interval measurements by seven ECG interpretation programs. J. Electrocardiol. 2020, 63, 75–82. [Google Scholar] [CrossRef] [Scilit]
- Angeli, F.; Verdecchia, P.; Angeli, E.; Poeta, F.; Sardone, M.; Bentivoglio, M.; Prosciutti, L.; Cocchieri, M.; Zollino, L.; Bellomo, G.; et al. Day-to-day variability of electrocardiographic diagnosis of left ventricular hypertrophy in hypertensive patients. Influence of electrode placement. J. Cardiovasc. Med. 2006, 7, 812–816. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mahendran, S.; Gupta, I.; Davis, J.; Davis, A.J.; Orchard, J.W.; Orchard, J.J. Comparison of methods for correcting QT interval in athletes and young people: A systematic review. Clin. Cardiol. 2023, 46, 1106–1115. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Phan, D.Q.; Silka, M.J.; Lan, Y.-T.; Chang, R.-K.R. Comparison of formulas for calculation of the corrected QT interval in infants and young children. J. Pediatr. 2015, 166, 960–964.e1-2. [Google Scholar] [CrossRef] [Scilit]
- Gervasi, S.F.; Bianco, M.; Palmieri, V.; Cuccaro, F.; Zeppilli, P. QTc Interval in Adolescents and Young Athletes: Influence of Correction Formulas. Int. J. Sports Med. 2017, 38, 729–734. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kligfield, P.; Gettes, L.S.; Bailey, J.J.; Childers, R.; Deal, B.J.; Hancock, E.W.; van Herpen, G.; Kors, J.A.; Macfarlane, P.; Mirvis, D.M.; et al. Recommendations for the standardization and interpretation of the electrocardiogram: Part I: The electrocardiogram and its technology a scientific statement from the American Heart Association Electrocardiography and Arrhythmias Committee, Council on Clinical Cardiology; the American College of Cardiology Foundation; and the Heart Rhythm Society endorsed by the International Society for Computerized Electrocardiology. J. Am. Coll. Cardiol. 2007, 49, 1109–1127. [Google Scholar] [CrossRef] [Scilit]
- Mason, J.W.; Ramseth, D.J.; Chanter, D.O.; Moon, T.E.; Goodman, D.B.; Mendzelevski, B. Electrocardiographic reference ranges derived from 79,743 ambulatory subjects. J. Electrocardiol. 2007, 40, 228–234. [Google Scholar] [CrossRef] [Scilit]
- de Alencar, J.N.; Monteiro, J.A.M.; Furtado, J.T.; Sacre, R.C.; Guerra, C.B.; Knoblauch, W.S.; Felicioni, S.P.; Scheffer, M.K.; De Marchi, M.F.N.; Franchini, K.G.; et al. ECG criteria for diagnosing left chambers disease in Pediatrics: The CHILDHEART study. J. Electrocardiol. 2025, 92, 154087. [Google Scholar] [CrossRef] [Scilit]
- Gregory, P.; Lodge, S.; Kilner, T.; Paget, S. Accuracy of ECG chest electrode placements by paramedics: An observational study. Br. Paramed. J. 2019, 4, 51–52. [Google Scholar] [CrossRef] [Scilit]
- Kayyali, M.; Mincholé, A.; Qian, S.; Young, A.; Ugurlu, D.; Fairweather, E.; Niederer, S.; Whitaker, J.; Bishop, M.; Lamata, P. Anatomical-electrical coupling of cardiac axes: Definitions and population variability for advancing personalised ECG interpretation. PLoS Comput. Biol. 2025, 21, e1013161. [Google Scholar] [CrossRef] [Scilit]
- Sanjo, K.; Hebiguchi, K.; Tang, C.; Rashed, E.A.; Kodera, S.; Togo, H.; Hirata, A. Sensitivity of Electrocardiogram on Electrode-Pair Locations for Wearable Devices: Computational Analysis of Amplitude and Waveform Distortion. Biosensors 2024, 14, 153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boggess, B.; Kindschi, K.; Friedman, E.; Boggess, S.; Berkoff, D. Electrocardiogram Lead Placement Accuracy and Its Implications on Universal Screening in Athletes. Cureus 2025, 17, e88076. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Makarov, L.M.; Kisileva, I.I.; Dolgikh, V.V.; Bimbaev, A.B.-Z.; Bairova, T.A.; Drozdova, A.I. Assesment of Parameters of QT Interval in Children and Adolescents. Kardiologiia 2006, 46, 37–41. [Google Scholar] [PubMed]
- Rodday, A.M.; Triedman, J.K.; Alexander, M.E.; Cohen, J.T.; Ip, S.; Newburger, J.W.; Parsons, S.K.; Trikalinos, T.A.; Wong, J.B.; Leslie, L.K. Electrocardiogram Screening for Disorders That Cause Sudden Cardiac Death in Asymptomatic Children: A Meta-analysis. Pediatrics 2012, 129, e999–e1010. [Google Scholar] [CrossRef] [Scilit]
- Alexander, M.E.; Gongwer, R.; Trachtenberg, F.L.; Minich, L.L.; Triedman, J.K.; Kaltman, J.R.; Czosek, R.J.; Tristani-Firouzi, M.; LaPage, M.J.; Tsao, S.S.; et al. Limited Relationship Between Echocardiographic Measures and Electrocardiographic Markers of Left Ventricular Size in Healthy Children. Pediatr. Cardiol. 2024, 45, 1055–1063. [Google Scholar] [CrossRef] [Scilit]
- Rivenes, S.M.; Colan, S.D.; Easley, K.A.; Kaplan, S.; Jenkins, K.J.; Khan, M.N.; Lai, W.W.; Lipshultz, S.E.; Moodie, D.S.; Starc, T.J.; et al. Usefulness of the pediatric electrocardiogram in detecting left ventricular hypertrophy: Results from the Prospective Pediatric Pulmonary and Cardiovascular Complications of Vertically Transmitted HIV Infection (P2C2 HIV) multicenter study. Am. Heart J. 2003, 145, 716–723. [Google Scholar] [CrossRef] [Scilit]
- Di Gioia, G.; Creta, A.; Campanale, C.M.; Fittipaldi, M.; Giorgino, R.; Quintarelli, F.; Satriano, U.; Cruciani, A.; Antinolfi, V.; Di Berardino, S.; et al. ECG is an inefficient screening-tool for left ventricular hypertrophy in normotensive African children population. PeerJ 2016, 4, e2439. [Google Scholar] [CrossRef] [Scilit]
- Czosek, R.J.; Cnota, J.F.; Knilans, T.K.; Pratt, J.; Guerrier, K.; Anderson, J.B. Relationship between echocardiographic LV mass and ECG based left ventricular voltages in an adolescent population: Related or random? Pacing Clin. Electrophysiol. 2014, 37, 1133–1140. [Google Scholar] [CrossRef] [Scilit]
- Snelder, S.M.; van de Poll, S.W.; de Groot–de Laat, L.E.; Kardys, I.; Zijlstra, F.; van Dalen, B.M. Optimized electrocardiographic criteria for the detection of left ventricular hypertrophy in obesity patients. Clin. Cardiol. 2020, 43, 483–490. [Google Scholar] [CrossRef] [Scilit]
- Khalaph, M.; Trajkovska, N.; Didenko, M.; Braun, M.; Imnadze, G.; Akkaya, E.; Fink, T.; Lucas, P.; Sciacca, V.; Beyer, S.; et al. A novel ECG algorithm for accurate localization of manifest accessory pathways in both children and adults: SMART-WPW. Heart Rhythm. 2025, 22, e738–e745. [Google Scholar] [CrossRef] [Scilit]
- Yoshinaga, M.; Ninomiya, Y.; Tanaka, Y.; Fukuyama, M.; Kato, K.; Ohno, S.; Horie, M.; Ogata, H. Holter Electrocardiographic Approach to Predicting Outcomes of Pediatric Patients With Long QT Syndrome. Circ. J. 2024, 88, 1176–1184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ban, M.M.; Iyer, V.R.; Nandi, D.; Vetter, V.L.; Banerjee, A. Reliability of Left Ventricular Hypertrophy by ECG criteria in Children with Syncope: Do the criteria need to be revised? Pediatr. Cardiol. 2016, 37, 722–727. [Google Scholar] [CrossRef] [Scilit]
- Christmyer, Z.; Pisupati, M.; Shah, M.J.; Srinivasan, C.; Vetter, V.L.; Iyer, V.R.; Triguba, M.; Janson, C.M. Risk Stratification in Pediatric Wolff-Parkinson-White: Practice Variation Among Pediatric Cardiologists and Electrophysiologists. Pediatr. Cardiol. 2024, 45, 1668–1675. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ogawa, Y.; Tanaka, T.; Kido, S. Maximum QTc on Holter electrocardiography in children. Pediatr. Int. 2018, 60, 507–512. [Google Scholar] [CrossRef] [Scilit]
- Buratti, G.; Shrestha, S.; Donne, M.; Katta, P. Approach to prolonged QT interval in paediatric and neonatal patients. Eur. J. Pediatr. 2025, 184, 778. [Google Scholar] [CrossRef] [Scilit]
- Chubb, H.; Campbell, R.M.; Motonaga, K.S.; Ceresnak, S.R.; Dubin, A.M. Management of Asymptomatic Wolff-Parkinson-White Pattern by Pediatric Electrophysiologists. J. Pediatr. 2019, 213, 88–95.e1. [Google Scholar] [CrossRef] [Scilit]
- Yıldırım, I.; Özer, S.; Karagöz, T.; Şahin, M.; Özkutlu, S.; Alehan, D.; Çeliker, A. Clinical and electrophysiological evaluation of pediatric Wolff-Parkinson-White patients. Anatol. J. Cardiol. 2015, 15, 485–490. [Google Scholar] [CrossRef] [Scilit]
- Bagkaki, A.; Parthenakis, F.; Chlouverakis, G.; Anastasakis, A.; Papagiannis, I.; Galanakis, E.; Germanakis, I. Epidemiology of Pediatric Cardiomyopathy in a Mediterranean Population. Children 2024, 11, 732. [Google Scholar] [CrossRef] [Scilit]
- Bagkaki, A.; Tsoutsinos, A.; Hatzidaki, E.; Tzatzarakis, M.; Parthenakis, F.; Germanakis, I. Mexiletine Treatment for Neonatal LQT3 Syndrome: Case Report and Literature Review. Front. Pediatr. 2021, 9, 674041. [Google Scholar] [CrossRef] [Scilit]
- Bagkaki, A.; Parthenakis, F.; Chlouverakis, G.; Galanakis, E.; Germanakis, I. Cardiovascular Disease Screening in Primary School Children. Children 2024, 12, 38. [Google Scholar] [CrossRef] [Scilit]
- Halasz, G.; Cattaneo, M.; Piepoli, M.; Romano, S.; Biasini, V.; Menafoglio, A.; Gasperetti, A.; Badini, M.; Villa, M.; Dall’Ara, L.; et al. Pediatric athletes’ ECG and diagnostic performance of contemporary ECG interpretation criteria. Int. J. Cardiol. 2021, 335, 40–46. [Google Scholar] [CrossRef] [Scilit]
- Petek, B.J.; Drezner, J.A.; Churchill, T.W. The International Criteria for Electrocardiogram Interpretation in Athletes: Common Pitfalls and Future Directions. Cardiol. Clin. 2023, 41, 35–49. [Google Scholar] [CrossRef] [Scilit]
- Bozkurt, B.; Germanakis, I.; Stylianou, Y. A study of time-frequency features for CNN-based automatic heart sound classification for pathology detection. Comput. Biol. Med. 2018, 100, 132–143. [Google Scholar] [CrossRef] [Scilit]
- Chatzakis, I.; Vassilakis, K.; Lionis, C.; Germanakis, I. Electronic health record with computerized decision support tools for the purposes of a pediatric cardiovascular heart disease screening program in Crete. Comput. Methods Programs Biomed. 2018, 159, 159–166. [Google Scholar] [CrossRef] [Scilit]



| Publication Year | Race/ethnicity of children | Study sample | Ages (years) | Echo confirmation of LVH | Sampling rate (Hz) | Filter settings (Hz) | QT correction formulas | ECG acquisition method | |
| Citation ⇣ | |||||||||
| [14] | 1980 | Caucasian (white) | 2141 | 0–16 | No | 333 | Not reported | Not reported | Auto & Visual * |
| [18] | 1990 | Caucasian (Scotland, UK) | 1780 | 0–16 | No | 500 | Not reported | Not reported | Automated |
| [6] | 2001 | Caucasian (predominantly) | 1912 | 0–16 | No | 1200 | ~320 | Not reported | Auto & Visual * |
| [19] | 2008 | Caucasian (Turkey) | 2241 | 0–16 | No | 500 | 0.05–150 | Bazett | Automated |
| [20] | 2018 | Caucasian (Netherlands) | 1011 | 0–18 | No | 250–500 | Automatic (not specified) | Bazett | Automated |
| [21] | 2018 | Asian (Japanese) | 16,773 | 6–15 | No | 500 | 0.5–35 | Custom vs Bazett | Auto & Visual * |
| [22] | 2019 | Caucasian (Turkey) | 1163 | 0-16 | No | 500 | Not reported | Bazett | Auto & Visual * |
| [7] | 2020 | North American, mixed race | 23,064 | 0–18 | No | 500 | Unfiltered | Bazett, Framingham, Friderica | Automated |
| [23] | 2021 | Eurasian, mixed race | 12,512 | 5–18 | Yes | 4000 | ≤150 | Bazett | Automated |
| [24] | 2022 | Caucasian (Polish) | 336 | 5–16 | No | 1000 | Not reported | Bazett | Auto & Visual * |
| [17] | 2023 | Asian (Taiwanese) | 1884 | 0–18 | No | 500 | Not reported | Not reported | Auto & Visual * |
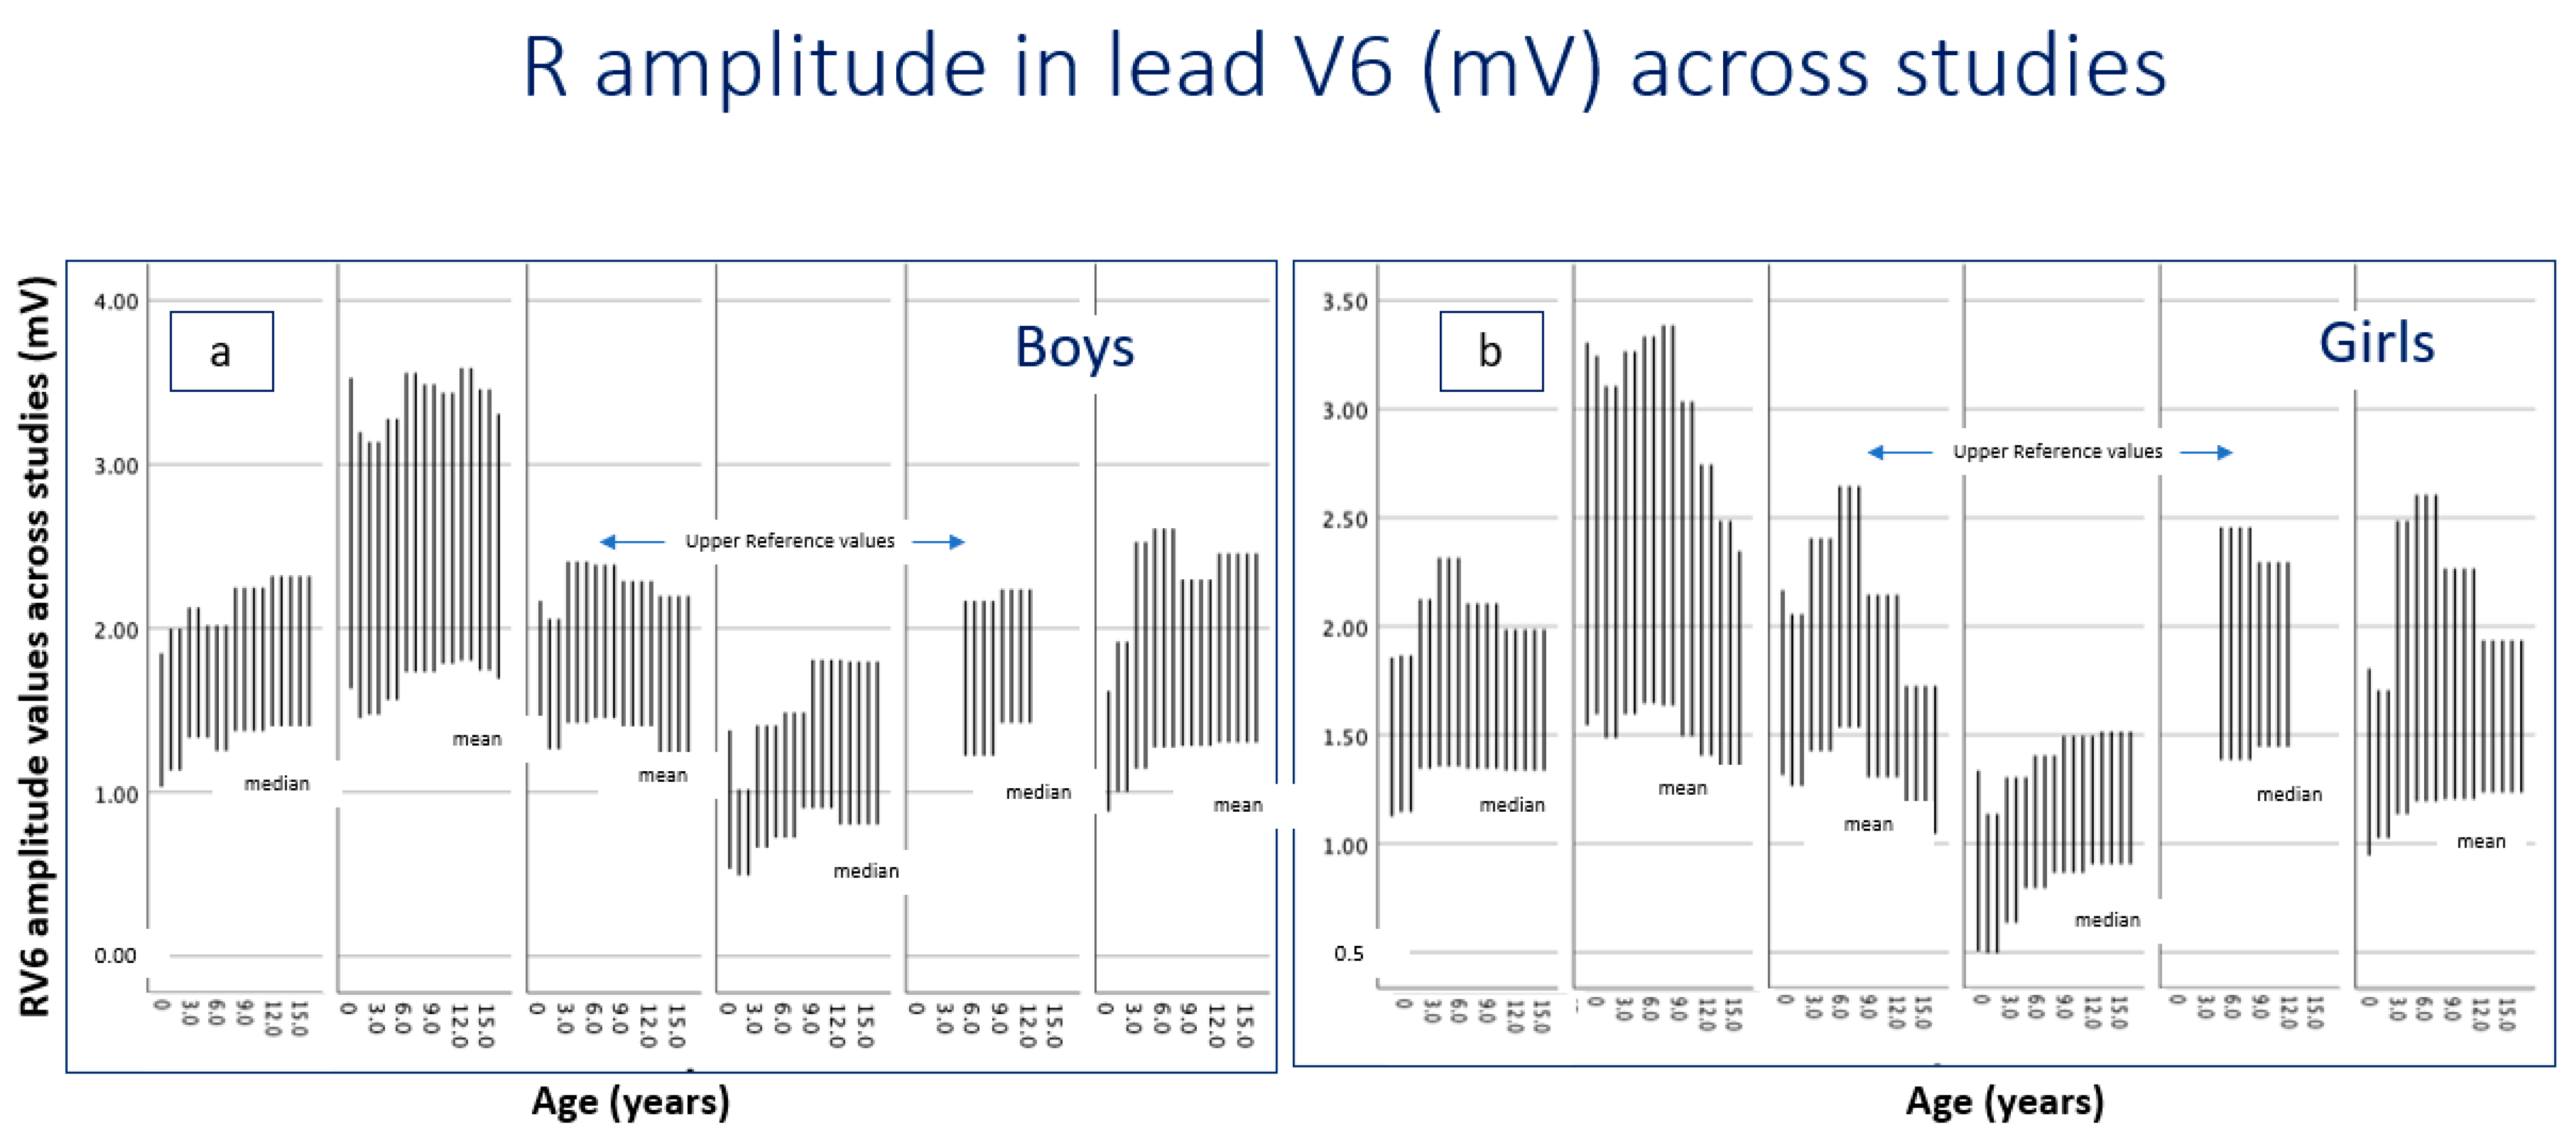
| Citation ⇢ | [14] | [6] | [7] | [17] | [22] | [24] | [19] | [21] | |||||||
| 98th percentile | 98th percentile | 99.5th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | ||||||||
| Age (years) ⇣ | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | |
| 0.5–1 | 2.0 | 1.84 | 1.85 | 3.52 | 3.3 | 2.16 | 2.16 | 1.37 | 1.33 | 1.61 | 1.8 | ||||
| 1 | 2.4 | 1.99 | 1.86 | 3.19 | 3.24 | 2.05 | 2.05 | 1.01 | 1.13 | 1.91 | 1.7 | ||||
| 2 | 2.4 | 1.99 | 1.86 | 3.13 | 3.10 | 2.05 | 2.05 | 1.01 | 1.13 | 1.91 | 1.7 | ||||
| 3 | 2.4 | 2.12 | 2.12 | 3.13 | 3.10 | 2.4 | 2.4 | 1.4 | 1.3 | 2.52 | 2.48 | ||||
| 4 | 2.4 | 2.12 | 2.12 | 3.27 | 3.26 | 2.4 | 2.4 | 1.4 | 1.3 | 2.52 | 2.48 | ||||
| 5 | 2.4 | 2.01 | 2.31 | 3.27 | 3.26 | 2.4 | 2.4 | 1.4 | 1.3 | 2.16 | 2.45 | 2.6 | 2.6 | ||
| 6 | 2.4 | 2.01 | 2.31 | 3.55 | 3.33 | 2.38 | 2.64 | 1.48 | 1.4 | 2.16 | 2.45 | 2.6 | 2.6 | 2.29 | 2.25 |
| 7 | 2.4 | 2.01 | 2.31 | 3.55 | 3.33 | 2.38 | 2.64 | 1.48 | 1.4 | 2.16 | 2.45 | 2.6 | 2.6 | ||
| 8 | 2.4 | 2.24 | 2.10 | 3.48 | 3.38 | 2.38 | 2.64 | 1.48 | 1.4 | 2.16 | 2.45 | 2.29 | 2.26 | ||
| 9 | 2.4 | 2.24 | 2.10 | 3.48 | 3.38 | 2.28 | 2.14 | 1.80 | 1.49 | 2.23 | 2.29 | 2.29 | 2.26 | ||
| 10 | 2.4 | 2.24 | 2.10 | 3.43 | 3.03 | 2.28 | 2.14 | 1.80 | 1.49 | 2.23 | 2.29 | 2.29 | 2.26 | ||
| 11 | 2.4 | 2.24 | 2.10 | 3.43 | 3.03 | 2.28 | 2.14 | 1.80 | 1.49 | 2.23 | 2.29 | 2.29 | 2.26 | ||
| 12 | 2.2 | 2.31 | 1.98 | 3.58 | 2.74 | 2.28 | 2.14 | 1.80 | 1.49 | 2.23 | 2.29 | 2.45 | 1.93 | 2.52 | 2.02 |
| 13 | 2.2 | 2.31 | 1.98 | 3.58 | 2.74 | 2.19 | 1.72 | 1.79 | 1.51 | 2.45 | 1.93 | ||||
| 14 | 2.2 | 2.31 | 1.98 | 3.45 | 2.48 | 2.19 | 1.72 | 1.79 | 1.51 | 2.45 | 1.93 | ||||
| 15 | 2.2 | 2.31 | 1.98 | 3.45 | 2.48 | 2.19 | 1.72 | 1.79 | 1.51 | 2.45 | 1.93 | 2.55 | 1.9 | ||
| 16 | 2.2 | 2.31 | 1.98 | 3.3 | 2.34 | 2.19 | 1.72 | 1.79 | 1.51 | 2.45 | 1.93 | ||||
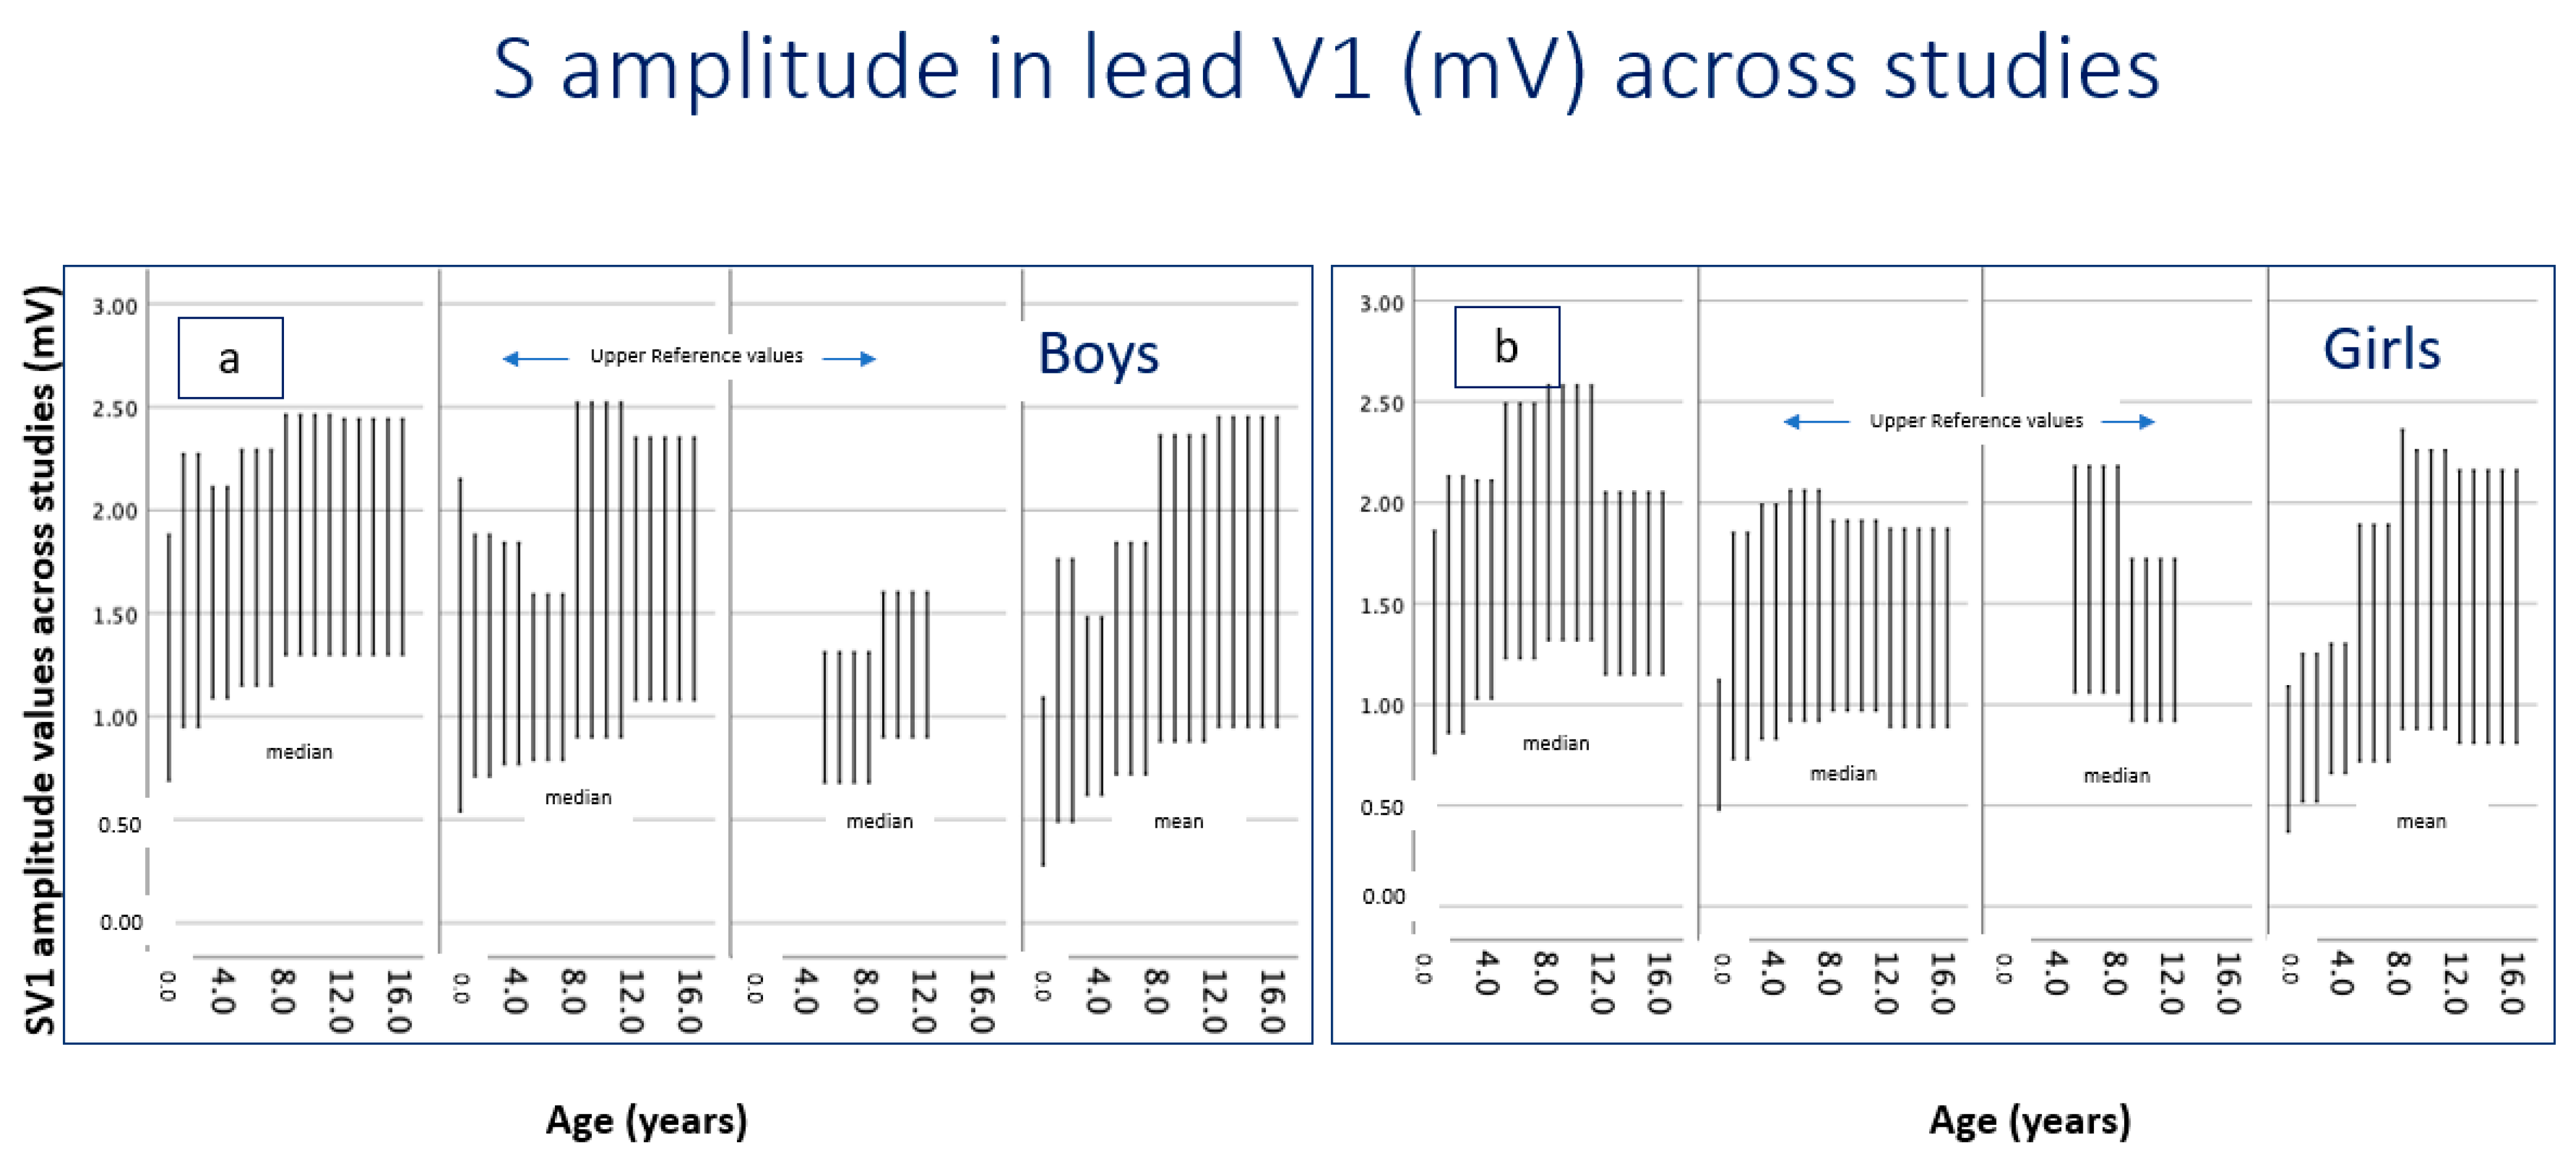
| Citation ⇢ | [14] | [6] | [19] | [22] | [24] | [21] | [17] | ||||||
| 98th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | |||||||
| Age (years) ⇣ | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | |
| 0.5–1 | 0.9 | 1.88 | 1.86 | 1.09 | 1.09 | 2.15 | 1.12 | 0.94 | 0.94 | ||||
| 1 | 0.8 | 2.27 | 2.13 | 1.76 | 1.25 | 1.88 | 1.85 | 1.25 | 1.25 | ||||
| 2 | 0.8 | 2.27 | 2.13 | 1.76 | 1.25 | 1.88 | 1.85 | 1.25 | 1.25 | ||||
| 3 | 0.8 | 2.11 | 2.11 | 1.48 | 1.3 | 1.84 | 1.99 | 1.25 | 1.25 | ||||
| 4 | 0.8 | 2.11 | 2.11 | 1.48 | 1.3 | 1.84 | 1.99 | 1.25 | 1.25 | ||||
| 5 | 0.8 | 2.29 | 2.49 | 1.84 | 1.89 | 1.59 | 2.06 | 1.31 | 2.18 | 1.25 | 1.25 | ||
| 6 | 0.8 | 2.29 | 2.49 | 1.84 | 1.89 | 1.59 | 2.06 | 1.31 | 2.18 | 2.25 | 2.29 | 1.56 | 1.38 |
| 7 | 0.8 | 2.29 | 2.49 | 1.84 | 1.89 | 1.59 | 2.06 | 1.31 | 2.18 | 1.56 | 1.38 | ||
| 8 | 0.8 | 2.46 | 2.58 | 2.36 | 2.36 | 2.52 | 1.91 | 1.31 | 2.18 | 1.56 | 1.38 | ||
| 9 | 0.8 | 2.46 | 2.58 | 2.36 | 2.26 | 2.52 | 1.91 | 1.6 | 1.72 | 1.49 | 1.43 | ||
| 10 | 0.8 | 2.46 | 2.58 | 2.36 | 2.26 | 2.52 | 1.91 | 1.6 | 1.72 | 1.49 | 1.43 | ||
| 11 | 0.8 | 2.46 | 2.58 | 2.36 | 2.26 | 2.52 | 1.91 | 1.6 | 1.72 | 1.49 | 1.43 | ||
| 12 | 0.8 | 2.44 | 2.05 | 2.45 | 2.16 | 2.35 | 1.87 | 1.6 | 1.72 | 2.57 | 2.22 | 1.49 | 1.43 |
| 13 | 0.8 | 2.44 | 2.05 | 2.45 | 2.16 | 2.35 | 1.87 | 1.5 | 1.5 | ||||
| 14 | 0.8 | 2.44 | 2.05 | 2.45 | 2.16 | 2.35 | 1.87 | 1.5 | 1.5 | ||||
| 15 | 0.8 | 2.44 | 2.05 | 2.45 | 2.16 | 2.35 | 1.87 | 2.87 | 1.97 | 1.5 | 1.5 | ||
| 16 | 0.8 | 2.44 | 2.05 | 2.45 | 2.16 | 2.35 | 1.87 | 1.5 | 1.5 | ||||
| Citation ⇢ | [6] | [7] | [23] | [19] | [22] | [17] | [21] | |||||||
| 2nd percentile | 0.5th percentile | 2nd percentile | 2nd percentile | 2nd percentile | 2nd percentile | 2nd percentile | ||||||||
| Age (years) ⇣ | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls |
| 0.5–1 | 82 | 88 | 79 | 77 | 78 | 70 | 72 | 72 | 91 | 91 | ||||
| 1 | 86 | 78 | 80 | 79 | 75 | 76 | 65 | 72 | 104 | 104 | ||||
| 2 | 86 | 78 | 84 | 83 | 75 | 76 | 65 | 72 | 104 | 104 | ||||
| 3 | 98 | 99 | 84 | 83 | 86 | 84 | 84 | 82 | 107 | 107 | ||||
| 4 | 98 | 99 | 90 | 87 | 86 | 84 | 84 | 82 | 107 | 107 | ||||
| 5 | 99 | 92 | 90 | 87 | 100 | 98 | 97 | 91 | 89 | 89 | 107 | 107 | ||
| 6 | 99 | 92 | 92 | 89 | 100 | 98 | 97 | 91 | 89 | 89 | 101 | 99 | 96 | 96 |
| 7 | 99 | 92 | 92 | 89 | 100 | 98 | 97 | 91 | 89 | 89 | 101 | 99 | ||
| 8 | 105 | 103 | 91 | 94 | 102 | 100 | 90 | 90 | 92 | 94 | 101 | 99 | ||
| 9 | 105 | 103 | 91 | 94 | 102 | 100 | 90 | 90 | 92 | 94 | 105 | 102 | ||
| 10 | 105 | 103 | 95 | 94 | 102 | 100 | 90 | 90 | 92 | 94 | 105 | 102 | ||
| 11 | 105 | 103 | 95 | 94 | 102 | 100 | 90 | 90 | 92 | 94 | 105 | 102 | ||
| 12 | 107 | 106 | 87 | 91 | 106 | 104 | 92 | 100 | 100 | 98 | 105 | 102 | 103 | 103 |
| 13 | 107 | 106 | 87 | 91 | 106 | 104 | 92 | 100 | 100 | 98 | 101 | 106 | ||
| 14 | 107 | 106 | 90 | 92 | 106 | 104 | 92 | 100 | 100 | 98 | 101 | 106 | ||
| 15 | 107 | 106 | 90 | 92 | 106 | 104 | 92 | 100 | 100 | 98 | 101 | 106 | 107 | 106 |
| 16 | 107 | 106 | 91 | 93 | 112 | 112 | 92 | 100 | 100 | 98 | 101 | 106 | ||
| Citation ⇢ | [6] | [7] | [23] | [19] | [22] | [17] | [21] | |||||||
| 98th percentile | 99.5th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | ||||||||
| Age (years) ⇣ | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls |
| 0.5–1 | 141 | 133 | 150 | 148 | 122 | 128 | 118 | 128 | 145 | 145 | ||||
| 1 | 151 | 147 | 151 | 150 | 146 | 158 | 147 | 146 | 148 | 148 | ||||
| 2 | 151 | 147 | 156 | 155 | 146 | 158 | 147 | 146 | 148 | 148 | ||||
| 3 | 152 | 153 | 156 | 155 | 150 | 158 | 156 | 140 | 151 | 151 | ||||
| 4 | 152 | 153 | 157 | 160 | 168 | 172 | 156 | 140 | 151 | 151 | ||||
| 5 | 160 | 156 | 157 | 160 | 160 | 158 | 168 | 172 | 151 | 161 | 151 | 151 | ||
| 6 | 160 | 156 | 161 | 160 | 160 | 158 | 168 | 172 | 151 | 161 | 163 | 160 | 159 | 158 |
| 7 | 160 | 156 | 161 | 160 | 160 | 158 | 172 | 178 | 151 | 161 | 163 | 160 | ||
| 8 | 174 | 163 | 170 | 162 | 168 | 164 | 172 | 178 | 204 | 151 | 163 | 160 | ||
| 9 | 174 | 163 | 170 | 162 | 168 | 164 | 172 | 178 | 204 | 151 | 163 | 167 | ||
| 10 | 174 | 163 | 172 | 173 | 168 | 164 | 172 | 178 | 204 | 151 | 163 | 167 | ||
| 11 | 174 | 163 | 172 | 173 | 168 | 164 | 172 | 178 | 170 | 184 | 163 | 167 | ||
| 12 | 178 | 176 | 155 | 154 | 174 | 172 | 184 | 174 | 170 | 184 | 163 | 167 | 173 | 177 |
| 13 | 178 | 176 | 155 | 154 | 174 | 172 | 184 | 174 | 170 | 184 | 179 | 176 | ||
| 14 | 178 | 176 | 157 | 157 | 174 | 172 | 184 | 174 | 170 | 184 | 179 | 176 | ||
| 15 | 178 | 176 | 157 | 157 | 174 | 172 | 184 | 174 | 170 | 184 | 179 | 176 | 186 | 186 |
| 16 | 178 | 176 | 163 | 160 | 184 | 176 | 184 | 174 | 170 | 184 | 179 | 176 | ||
| Citation ⇢ | [6] | [7] | [23] | [20] | [19] | [22] | [17] | [21] | ||||||||
| 98th percentile | 99.5th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | |||||||||
| Age (years) ⇣ | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls |
| 0.5–1 | 86 | 80 | 101 | 107 | 303 | 303 | 94 | 90 | 92 | 94 | 98 | 98 | ||||
| 1 | 88 | 85 | 105 | 101 | 303 | 303 | 100 | 100 | 92 | 106 | 106 | 106 | ||||
| 2 | 88 | 85 | 115 | 103 | 322 | 322 | 100 | 100 | 92 | 106 | 106 | 106 | ||||
| 3 | 92 | 88 | 115 | 103 | 322 | 322 | 98 | 98 | 100 | 102 | 106 | 106 | ||||
| 4 | 92 | 88 | 125 | 114 | 348 | 348 | 98 | 98 | 100 | 102 | 108 | 108 | ||||
| 5 | 98 | 95 | 125 | 114 | 104 | 98 | 348 | 348 | 108 | 100 | 99 | 105 | 108 | 108 | ||
| 6 | 98 | 95 | 118 | 115 | 104 | 98 | 371 | 371 | 108 | 100 | 99 | 105 | 108 | 108 | 100 | 95 |
| 7 | 98 | 95 | 118 | 115 | 104 | 98 | 371 | 371 | 108 | 100 | 99 | 105 | 118 | 100 | ||
| 8 | 103 | 99 | 122 | 115 | 106 | 102 | 371 | 371 | 106 | 100 | 100 | 116 | 118 | 100 | ||
| 9 | 103 | 99 | 122 | 115 | 106 | 102 | 371 | 371 | 106 | 100 | 100 | 116 | 118 | 100 | ||
| 10 | 103 | 99 | 119 | 116 | 106 | 102 | 395 | 395 | 106 | 100 | 100 | 116 | 107 | 105 | ||
| 11 | 103 | 99 | 119 | 116 | 106 | 102 | 395 | 395 | 106 | 100 | 100 | 116 | 107 | 105 | ||
| 12 | 111 | 106 | 123 | 110 | 108 | 110 | 395 | 395 | 108 | 108 | 102 | 114 | 107 | 105 | 109 | 103 |
| 13 | 111 | 106 | 123 | 110 | 108 | 110 | 395 | 395 | 108 | 108 | 102 | 114 | 120 | 108 | ||
| 14 | 111 | 106 | 124 | 112 | 108 | 110 | 414 | 414 | 108 | 108 | 102 | 114 | 120 | 108 | ||
| 15 | 111 | 106 | 124 | 112 | 108 | 110 | 414 | 414 | 108 | 108 | 102 | 114 | 120 | 108 | 115 | 105 |
| 16 | 111 | 106 | 124 | 114 | 114 | 106 | 426 | 426 | 108 | 108 | 102 | 114 | 120 | 108 | ||
| Citation ⇢ | [6] | [7] | [23] | [20] | [19] | [22] | [17] | |||||||
| 98th percentile | 99.5th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | 98th percentile | ||||||||
| Age (years) ⇣ | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls | Boys | Girls |
| 0.5–1 | 449 | 446 | 499 | 499 | 432 | 432 | 489 | 482 | 429 | 435 | 334 | 334 | ||
| 1 | 455 | 447 | 491 | 489 | 432 | 432 | 490 | 480 | 441 | 436 | 363 | 363 | ||
| 2 | 455 | 447 | 492 | 487 | 426 | 426 | 490 | 480 | 441 | 436 | 363 | 363 | ||
| 3 | 448 | 442 | 492 | 487 | 426 | 426 | 483 | 470 | 431 | 427 | 374 | 374 | ||
| 4 | 448 | 442 | 494 | 484 | 427 | 427 | 483 | 470 | 431 | 427 | 374 | 374 | ||
| 5 | 443 | 449 | 494 | 484 | 465 | 463 | 427 | 427 | 464 | 465 | 433 | 435 | 374 | 374 |
| 6 | 443 | 449 | 487 | 484 | 465 | 463 | 431 | 431 | 464 | 465 | 433 | 435 | 386 | 384 |
| 7 | 443 | 449 | 487 | 484 | 465 | 463 | 431 | 431 | 464 | 465 | 433 | 435 | 386 | 384 |
| 8 | 440 | 447 | 488 | 483 | 465 | 467 | 431 | 431 | 474 | 486 | 441 | 442 | 386 | 384 |
| 9 | 440 | 447 | 488 | 483 | 465 | 467 | 431 | 431 | 474 | 486 | 441 | 442 | 383 | 379 |
| 10 | 440 | 447 | 485 | 492 | 465 | 467 | 435 | 435 | 474 | 486 | 441 | 442 | 383 | 379 |
| 11 | 440 | 447 | 485 | 492 | 465 | 467 | 435 | 435 | 474 | 486 | 441 | 442 | 383 | 379 |
| 12 | 449 | 457 | 486 | 488 | 464 | 468 | 435 | 435 | 473 | 486 | 433 | 436 | 383 | 379 |
| 13 | 449 | 457 | 486 | 488 | 464 | 468 | 435 | 435 | 473 | 486 | 433 | 436 | 403 | 412 |
| 14 | 449 | 457 | 481 | 487 | 464 | 468 | 440 | 440 | 473 | 486 | 433 | 436 | 403 | 412 |
| 15 | 449 | 457 | 481 | 487 | 464 | 468 | 440 | 440 | 473 | 486 | 433 | 436 | 403 | 412 |
| 16 | 449 | 457 | 480 | 490 | 454 | 466 | 440 | 440 | 473 | 486 | 433 | 436 | 403 | 412 |
| ECG Finding | Borderline Values | Recommended Follow-Up | References |
|---|---|---|---|
| Left Ventricular Hypertrophy (LVH) | Precordial R- or S-wave amplitude near the 98th percentile (age/sex-specific values) |
| [6,52] |
| QTc Prolongation (Long QT Syndrome) | Borderline: 440–460 ms Prolonged: >460 ms High suspicion: >480 ms (age/sex-specific values) |
| [51,54,55] |
| Pre-excitation/ WPW Pattern | Short PR interval with delta wave, and normal or prolonged QRS (age/sex-specific values) |
| [53,56,57] |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Miliaraki, M.; Germanakis, I. Pediatric Electrocardiogram in Preparticipation Screening: Narrative Review of Normal Values in Key Features. Children 2026, 13, 209. https://doi.org/10.3390/children13020209
Miliaraki M, Germanakis I. Pediatric Electrocardiogram in Preparticipation Screening: Narrative Review of Normal Values in Key Features. Children. 2026; 13(2):209. https://doi.org/10.3390/children13020209
Chicago/Turabian StyleMiliaraki, Marianna, and Ioannis Germanakis. 2026. "Pediatric Electrocardiogram in Preparticipation Screening: Narrative Review of Normal Values in Key Features" Children 13, no. 2: 209. https://doi.org/10.3390/children13020209
APA StyleMiliaraki, M., & Germanakis, I. (2026). Pediatric Electrocardiogram in Preparticipation Screening: Narrative Review of Normal Values in Key Features. Children, 13(2), 209. https://doi.org/10.3390/children13020209