


Abstract
Robotic assistance in minimally invasive surgery has significantly improved precision and dexterity; however, many supportive tasks, such as blood aspiration, still rely on manual operation. This work presents the design and implementation of a supervised autonomous robotic aspirator for detecting and removing bleeding in an in vitro experimental model. The proposed system integrates a perception module based on a convolutional neural network for real-time blood segmentation, a task planner for high-level action execution, and a control strategy based on artificial potential fields for autonomous navigation. Additionally, a mixed-reality human–robot interaction interface is incorporated to enable system supervision and seamless transition to teleoperation when required. The system was experimentally validated with a set of in vitro experiments under three representative bleeding scenarios, evaluating four suction strategies based on the computation method for the target selection. Results demonstrate high blood removal rates (above 80% in all cases) and high suction efficiency. The comparative analysis reveals that the performance of the suction strategies is scenario-dependent and highlights a trade-off between suction efficiency and removed area. These findings support the feasibility of autonomous robotic aspiration and provide insights into the design of adaptive strategies for surgical assistance, contributing toward increased task autonomy and reduced need for continuous manual suction control during minimally invasive procedures.
1. Introduction
Robotic assistance has become a fundamental component of modern minimally invasive surgery, enabling enhanced precision, tremor filtering, and improved dexterity compared with conventional laparoscopy. Robotic platforms such as the da Vinci Surgical System have achieved widespread clinical adoption, with more than 8600 systems installed worldwide and over 14 million procedures performed to date. Despite these advances, the predominant paradigm in robotic surgery remains master–slave teleoperation, in which the surgeon directly controls the surgical instruments while repetitive supportive tasks are still performed manually. For this reason, a growing research trend in medical robotics focuses on introducing increasing levels of autonomy into surgical assistants in order to reduce surgeon workload and improve workflow efficiency [1].
Early efforts in surgical automation have primarily addressed supportive tasks that exhibit a high degree of standardization. Among them, endoscope guidance has received considerable attention, as it is a simple task that can reduce surgeon cognitive load while maintaining a stable visual field. Several approaches have been proposed based on explicit surgeon commands, including voice interfaces [2], head-motion tracking [3], and gaze-based control [4]. Although these solutions eliminate the need for a human assistant, they still require continuous attention from the surgeon to guide the camera. More recently, research has explored camera guidance approaches in which the robot directly analyzes the surgical scene. Vision-based strategies that track surgical instruments have demonstrated the potential of this paradigm by endowing the robot with greater autonomy without continuous supervision by the surgeon [5,6,7].
Other surgical tasks that have been subject to automation are those common to a wide range of surgical procedures, and that exhibit a high degree of standardization, such as organ or tissue retraction [8,9,10], suturing [11,12,13], and knot tying [14]. These works demonstrate that automating supportive tasks can significantly streamline the surgical workflow.
Within this context, intraoperative blood aspiration represents a particularly suitable candidate for automation. During minimally invasive procedures, the accumulation of blood can rapidly degrade the visual field and obscure critical anatomical structures, requiring a human assistant to manually operate a suction tool to remove blood. This manual intervention introduces variability and coordination challenges that an autonomous robotic counterpart could mitigate. Previous studies have demonstrated that semi-autonomous suction can improve surgical performance by preventing states of high cognitive demand on the main surgeon [15]. However, achieving autonomous blood aspiration requires the integration of multiple technological challenges that need to be addressed: a robust real-time blood detection algorithm, a safe control strategy, and an efficient trajectory generation to optimize suction.
Several works have addressed automated blood removal. Richter et al. proposed an autonomous suction framework for detecting and removing blood using the da Vinci Research Kit, incorporating an autonomous trajectory generation based on temporal information (pixel age) to prioritize active bleeding regions [16]. Ou et al. tested a reinforcement learning strategy for rinsing and cleaning surgical fields [17]. Their approach is based on customized simulation environments, where two autonomous agents are trained using robot learning approaches and transferred to the real world. Although the results are very promising, depth information, inherent to real surgical scenarios, is not considered in this work. Barragan et al. studied the surgeon workload with a semi-autonomous suction robotic assistant [15]. They computed the centroids and areas of detected blood blobs using a fully convolutional model. Then, a straight-line trajectory from the current position to the calculated target position was calculated and executed by the robot. In this work, collision avoidance is not directly addressed; instead, the surgeon is advised of the robot’s target position to avoid the collision.
From the perception perspective, automatic bleeding detection in endoscopic imagery has significantly advanced in recent years. Early approaches relied on color filtering and handcrafted features [18], whereas modern methods predominantly employ deep learning models. Convolutional neural networks (CNNs) have demonstrated strong performance in detecting bleeding in laparoscopic videos. Horita et al. developed a YOLOv7-based detector capable of identifying active bleeding in real time during laparoscopic procedures [19]. Similarly, Hua et al. have proposed a hybrid spatiotemporal architecture combining RGB images and optical flow to improve robustness in dynamic surgical scenes [20]. Rabbani et al. have also proposed a ResNet-50-based space-time memory network with positional encoding for video-based bleeding source segmentation via adversarial domain adaptation between real and synthetic data [21].
In addition to perception, autonomous navigation of surgical instruments poses unique challenges due to the constraints of laparoscopic manipulation. Learning-based motion planning strategies, such as Deep Reinforcement Learning (DRL), have been explored for complex robotic manipulation tasks [22,23]. However, these approaches typically require large datasets and extensive training procedures, and they often lack the transparency and predictability required for safety-critical medical applications. Alternatively, deterministic motion planning techniques are attractive alternatives for surgical robotics. Among them, Artificial Potential Fields (APF), originally formulated by Khatib [24], provide a computationally efficient method for reactive navigation by combining attractive forces toward the goal and repulsive forces from obstacles.
The APF algorithm is based on the generation of artificial potential fields in Cartesian space, where the goal location induces an attractive force and obstacles generate repulsive forces that influence the robot motion. This technique is widely applied in robotic applications for obstacle avoidance [25,26], providing real-time low-level path planning and control. APF-based strategies have also demonstrated strong performance in scenarios involving dual-arm manipulators, enabling stabilized motion planning with smoother trajectories and optimized spatial separation [27]. These characteristics make APFs particularly suitable for MIS applications, where instruments operate within a confined workspace and unexpected collisions between instruments or with surrounding anatomical structures may occur. In this context, Tang et al. proposed an APF method for master-slave surgical robots in which virtual fixtures are automatically generated based on marked points by the surgeon before the intervention [28]. Similarly, Hao et al. proposed a novel path planning algorithm for surgical robots based on APFs to guide the tool to the goal position and a primal-dual neural network to minimize the angular velocity [29].
Motivated by these challenges, this work proposes an autonomous surgical robotic aspirator with a mixed-reality HRI interface for human supervision. An overview of this scenario is illustrated in Figure 1, showing a conventional minimally invasive procedure augmented with a robotic aspirator for autonomous blood removal. The system consists of a suction tool attached to an external robot, enabling autonomous control of the instrument. Supervision of the robot’s performance is done through a human–robot interaction (HRI) interface, consisting of a virtual reality (VR) headset for visualizing the intraoperative endoscopic image. Relevant information regarding the intervention and the performance of the robotic aspirator is overlaid onto the endoscopic view within a mixed-reality (MR) environment. This concept is applicable for either manual or robot-assisted management of the surgical tools, controlled by the main surgeon.
Figure 1.
Overview of the surgical scenario proposed in this work. A conventional minimally invasive procedure is augmented with an autonomous robotic aspirator for blood removal without direct human control. Supervision of the system is performed through a human–robot interaction (HRI) interface, consisting of a VR headset to visualize the endoscopic image and a haptic controller for robot teleoperation if necessary.
Thus, the main contributions of this paper are:
- The design and experimental validation of a unified autonomous robotic aspiration framework for minimally invasive surgery, integrating perception, task planning, autonomous navigation, and suction control within a single operational system.
- The formulation and comparative evaluation of multiple centroid-based target selection strategies for autonomous blood aspiration, together with an analysis of their spatial discrepancy and its influence on robotic navigation behavior under different bleeding scenarios.
- A systematic experimental assessment under representative bleeding scenarios, demonstrating the scenario-dependent behavior of the evaluated suction strategies and revealing the trade-off between suction efficiency and blood removal performance.
The paper is organized as follows. Section 2 describes the overall system architecture and details the bleeding detection and autonomous navigation algorithms. This section concludes with the experimental software and hardware experimental setup used for the validation of the system, along with the experimental design. Section 3 analyzes the experimental results and a discussion is presented in Section 4. Finally, Section 5 summarizes the conclusions of the work.
2. Material and Methods
Figure 2 shows the overall system architecture and workflow of the autonomous robotic aspirator proposed in this work. First, endoscopic images are processed in the perception layer, which performs blood segmentation using a pretrained convolutional neural network (CNN) that outputs a mask of the detected blood regions. Then, region analysis is performed to compute the following blood descriptors for each region: (1) the area, used to filter small blood regions and to control suction deactivation, (2) the centroid, which is used as candidate targets for tool navigation, and (3) a temporal persistence map, which represents the age of the blood and gives an idea of the blood flow.
Figure 2.
Overall system architecture and workflow of the autonomous robotic aspirator. The system processes endoscopic images for blood segmentation and region analysis, which are used by the task planner to generate the high-level navigation and suction actions to control the robotic aspirator. Human supervision is provided through a mixed-reality HRI interface, enabling direct robot teleoperation when necessary.
Based on this information, the task planner generates the high-level navigation and suction actions. The mode selector module allows switching from autonomous navigation (task planner input) or teleoperation (haptic controller input) in case of emergency. Navigation towards a target position is implemented through a local planner based on an Artificial Potential Field (APF) approach to generate collision-free trajectories towards the target blood region while avoiding interactions with other surgical instruments and anatomical structures, such as organs or suturing needles. Robot low-level controller ensures that the tool motion satisfies the remote-center-of-motion (RCM) constraint imposed by the fulcrum point. Once the tool reaches the target position, the suction control module activates the suction tool. The system then monitors the area of the target region and deactivates suction once the blood has been removed.
To ensure safety, human supervision is provided through a human–robot interaction (HRI) interface. In this work, we propose a mixed-reality (MR) supervisory console based on a virtual reality (VR) headset and a haptic controller. Within the headset, the virtual environment is replaced by a real-time video stream captured by the laparoscopic endoscope, allowing the operator to directly visualize the intraoperative scene. This view is augmented with overlaid information about the scene (detected blood regions) and system performance (triggered high-level actions). The interface enables both passive supervision and direct teleoperation. Under normal operation, the robotic aspirator performs the task autonomously while the human assistant supervises its behavior through the HRI interface. If necessary, the operator can take direct control of the instrument by switching to teleoperation mode using a button on the haptic controller. In this mode, instrument motion is controlled through the hand motions of the controller, allowing intuitive manipulation of the tool. The objective of the proposed HRI interface in this work is to provide a supervisory and teleoperation mechanism integrated within the autonomous robotic aspiration framework. Moreover, it also acts as a supervisory safety mechanism, allowing the operator to immediately switch from autonomous mode to teleoperation if unexpected robot behavior or perception failures are detected. A detailed description of the mixed-reality interface design and interaction paradigm is beyond the scope of the present paper and can be found in [30].
2.1. Blood Segmentation and Region Analysis
The perception pipeline is summarized in Figure 3. For blood segmentation, we employ a CNN based on the U-Net architecture, a well-established model for medical image segmentation [31]. This architecture is particularly suitable due to its ability to capture both global and local features, enabling precise blood segmentation. For each incoming endoscopic frame , the CNN model produces a pixel-wise probability map indicating the likelihood of blood presence. During inference, the U-Net blood-probability map is converted into a binary blood mask, , using a post-inference binarization threshold .
Figure 3.
Perception layer pipeline. Endoscopic Images are processed by a CNN to obtain a blood mask . Then, candidate blood regions are analyzed to extract a descriptive tuple containing their area, a temporal persistence map and their centroid.
This binary mask is then analyzed to extract descriptive features for each detected blood region, which are aggregated into a blood descriptor tuple as:
where r denotes the region identifier, is the area of the region, represents the 3D coordinates of its centroid with respect to the camera, and is the temporal persistence descriptor encoding the age of the region pixels.
First, to improve robustness against noise and small artifacts, area filtering is applied to the mask: regions whose area is smaller than a predefined threshold are discarded to avoid spurious detections. In addition to spatial information, the algorithm maintains a temporal persistence map , which accumulates the number of consecutive frames in which each pixel i is classified as blood. This allows the system to estimate the temporal age of bleeding regions and distinguish persistent bleeding from transient artifacts. Then, the maximum persistence value within each region is computed as:
This value is used by the task planner to prioritize blood regions in the presence of simultaneous bleeding.
Finally, the 3D centroid of each blood region, , is transformed into the robot frame and used as the target location for the navigation action. As this position evolves with blood flow and progressive removal, it defines the dynamic trajectory of the aspirator. Thus, different centroid definitions can be employed, resulting in different suction strategies: while a geometric centroid provides a purely spatial estimate, a persistence-weighted centroid—computed based on pixel age—guides the target towards either the bleeding source (older pixels) or the region boundaries. In this work, we explore both approaches (see Section 2.5.2) to evaluate their impact on the suction strategy.
The centroid is initially computed in the 2D image space, as shown in Figure 4, which illustrates the complete geometric model of the system. The 3D centroid is obtained by back-projecting the image coordinates using the pinhole camera model of an RGB-D camera as:
where Z corresponds to the depth value at the centroid location, are the focal lengths in pixels, and denote the optical center of the camera. The transformation from the camera frame C to the robot base frame R is detailed in Section 2.2.
Figure 4.
Geometric model of the system. The 2D image centroid is deprojected into 3D space as using depth information from the RGB-D camera. This position is transformed from the camera reference frame into the robot base frame to guide the suction tool tip, .
2.2. Task Planner
The task planner triggers the system high-level actions, namely navigation toward a target position (NavigateTo(pos)) and suction activation or deactivation (Suction(on/off)). The task planner workflow is described in Algorithm 1. When the perception layer identifies blood regions in the image, whose descriptors are stored in , the blood region with the largest area is selected as the target region to be removed (), i.e.:
| Algorithm 1: Task planner workflow |
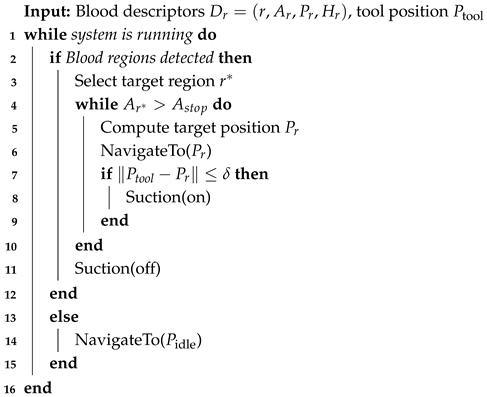 |
While blood of the target region remains, i.e., is larger than a certain threshold , the system continuously updates the descriptor of the selected region , i.e., , and computes the target position used to navigate the robot, as:
where is the homogeneous transformation between the camera reference frame and the robot base frame . A navigation command is then issued to guide the suction tool toward (note that the low-level control is handled by the control layer; see Section 2.3). The system evaluates the distance between the tool tip, , and the target position and activates suction when , being a certain distance threshold. Once the target blood region has been removed, suction is deactivated. If no blood regions are detected, the robot is commanded to move to its idle position.
2.3. Autonomous Navigation Method
Figure 5 illustrates the implementation of the navigation toward a target position action (NavigateTo(pos)). The local planner takes as input the target location of the blood region to be removed, , and generates the desired reference position for the robot, . The low-level controller then maps this reference into the corresponding robot end-effector position, , while enforcing the remote center of motion (RCM) constraint imposed by the fulcrum point, which is inherent to minimally invasive procedures. This autonomous navigation mode can be switched to teleoperation mode through the haptic controller of the HRI interface.
Figure 5.
Control architecture of the proposed autonomous navigation method based on artificial potential fields, including low-level remote center of motion (RCM) control of the robot, and integration of the teleoperation mode through the haptic controller of the HRI.
The local planner to guide the suction tool toward the target position is performed through Artificial Potential Fields (APF). This is a motion planning method in which the robot is guided by an artificial potential function defined over the workspace. Thus, the robot moves under the influence of a virtual force derived from this potential, which attracts it toward the goal and repels it away from obstacles.
Let denote the current position of the suction tool tip, and the desired target position. The attractive potential is defined as a quadratic function of the distance to the goal:
where is a positive scalar gain that determines the strength of the attractive potential toward the goal. The repulsive potential associated with the m-th obstacle is defined as:
where is a positive gain that determines how strongly the robot is pushed away from obstacles, is the distance between the robot tool tip and the m-th obstacle, and is the obstacle influence radius. The total potential field is defined as the sum of the attractive and repulsive contributions:
The robot motion is driven by the negative gradient of the potential field. In this work, a kinematic formulation is adopted, where the commanded velocity of the tool tip is defined as:
Therefore, the desired position of the tool tip, , commanded to the low-level controller of the robot is computed as:
In practice, several known limitations of classical APF methods are alleviated in the proposed implementation. In particular, oscillatory behavior near the goal and excessive velocities are reduced by introducing a dead zone around the target and saturating the commanded velocity. Additionally, robustness against outdated visual references is improved through a timeout mechanism that prevents the robot from reacting to stale target updates. The present implementation incorporates both attractive and repulsive APF components for target convergence and obstacle avoidance. However, the problem of obstacle-induced local minima was not explicitly addressed in the current framework and remains part of future work.
Finally, the desired reference position is then transformed into the corresponding command of the robot end-effector, , considering the RCM constraints imposed by the fulcrum position, . Estimation of this position is implemented following the algorithm described in our previous work [32], which relies on the wrench, measured by a force/torque sensor at the end-effector of the robot, . In that work, the RCM control framework was experimentally evaluated under different initial fulcrum-distance estimation errors, including perturbations up to several centimeters, demonstrating the capability of the force-position controller to compensate for such deviations during laparoscopic manipulation. In this work, we have adopted the same control framework and laboratory setup.
2.4. Experimental Setup
The experimental setup implemented in this work is illustrated in Figure 6. The robotic aspirator was implemented using a UR3 robot (Universal Robots, Odense, Denmark) together with a conventional surgical aspirator donated by the Hospital Materno-Infantil of Málaga (Spain), which was modified to allow automatic activation and deactivation of the suction process.
Figure 6.
Experimental setup of the proposed robotic aspirator system. (a) The robotic aspirator consists of a conventional surgical aspirator modified to allow automatic activation and deactivation and to be mounted onto the end-effector of a UR3e robotic arm. The vision system is an RGB-D camera mounted onto a second robot. (b) The supervisory interface is implemented using the VR Meta Quest 3 platform, which consists of a VR headset for visualization and a haptic controller to interact with the system.
To automate the suction process, a solenoid valve (model ST-DA brass FKM, JP Fluid Control, Tameson, Eindhoven, The Netherlands) controlled by a microcontroller Arduino Nano ESP32 (Arduino SA, Lugano, Switzerland) was integrated into the system. The solenoid valve is connected on one side to the laparoscopic suction tool and on the other side to a suction pump (New Aspiret, CA-MI, Italy), allowing the suction flow to be automatically activated or deactivated through commands generated by the ESP32. To integrate the suction mechanism with the robotic manipulator, a dedicated tool adapter was designed. This component, shown in Figure 6a, includes an internal cavity to house the solenoid valve and an outlet port for the suction tool. The rear part of the adapter is designed to be mechanically attached to the robot end effector, enabling the robot to manipulate the suction tool. Although the perception system was quantitatively evaluated using real surgical images (see Section 3.1), artificial bleeding was employed for laboratory experimentation. Bleeding was simulated using a custom-made fluid composed of water, milk, glycerin, and red dye, contained in a transparent reservoir. The artificial fluid was designed to provide a visually representative bleeding appearance for perception and aspiration experiments, rather than to accurately reproduce the rheological properties of human blood. In particular, viscosity, non-Newtonian behavior, and clot formation effects were not explicitly modeled in the present study.
As the vision system, an Intel RealSense D405 RGB-D camera (Intel Corporation, Santa Clara, CA, USA, USA) was used. This device provides both RGB images and depth information by combining two infrared sensors for stereo vision with an infrared projector. The camera offers a maximum RGB resolution of 1920 × 1080 pixels and a depth resolution of 1280 × 720 pixels, with a frame rate of up to 30 frames per second. The depth sensing range extends approximately from 0.2 m to 10 m, making it suitable for close-range perception tasks in the experimental surgical setup. The RGB-D camera is mounted on a second robot in order to facilitate the computation of the homogeneous transformation between the camera reference frame and the robot base frame, of Equation (5).
As shown in Figure 6b, the supervisory interface was implemented using the Meta Quest 3 platform. The headset provides a per-eye resolution of 2064 × 1920 pixels and a refresh rate of 90 Hz, enabling real-time visualization of the surgical field. The handheld controllers provide six degrees of freedom and include inertial sensors and programmable buttons, which are used to trigger teleoperation and to enable aspirator suction in this mode. The scene information integrated into the HRI interface includes:
- Navigation: on/off. This indicator informs the human assistant that a bleeding region has been detected and that the system has initiated tool navigation towards the target position.
- Suction: on/off. This indicator is set to on when the suction tool is activated, and to off otherwise.
The software integration of the different modules of the system was implemented using the Robot Operating System (ROS) as the common middleware platform. The mixed-reality application that merges the image from the vision system and the scene information for the HRI interface was developed in the Unity environment and deployed on the Meta Quest 3 headset. The integration with the rest of the system was implemented using a ROS bridge server to subscribe to the system topics, and a ROSConnection plugin to publish the information from the haptic controller.
2.5. Evaluation Methodology
Evaluation of the autonomous robotic aspirator proposed in this work was carried out following a twofold approach: (i) assessment of the bleeding segmentation module using real surgical images, and (ii) evaluation of the overall system performance in an in vitro scenario. Although these two evaluations correspond to different visual domains, the same U-Net model trained on gynecological images was used during the online in vitro robotic experiments. No additional detector, retraining, fine-tuning, or domain-specific threshold adjustment was applied to the laboratory scene. The post-inference threshold was kept fixed at , matching the operating point selected during the offline segmentation analysis.
2.5.1. Blood Segmentation Evaluation
The blood segmentation module was implemented using a vanilla U-Net architecture for binary semantic segmentation. The segmentation dataset used in this work corresponds to the publicly available annotated bleeding-image subset described by Rabbani et al. [21]. It consists of 750 gynecological laparoscopic surgery images with pixel-level blood-region masks, annotated by junior surgeons under the supervision of senior surgeons. The network receives RGB endoscopic images resized to and outputs a single-channel probability map representing the likelihood of blood presence at each pixel. The encoder consists of four downsampling stages with 64, 128, 256, and 512 filters, respectively, followed by a bottleneck layer with 1024 filters. Each stage includes two convolutional layers with ReLU activation and max-pooling. The decoder follows a symmetric structure with skip connections between encoder and decoder stages. The output layer consists of a convolution with sigmoid activation. No batch normalization, dropout layers, or pretrained encoder were used. The model was trained using Binary Cross-Entropy loss and the Adam optimizer with a learning rate of . Training was conducted for 45 epochs with a batch size of 16 on an NVIDIA Tesla V100 GPU (32 GB). The dataset was split at image level into training, validation, and test subsets using proportions of 80%, 10%, and 10%, respectively. Data augmentation was limited to horizontal flipping, and all images and masks were resized to pixels.
During inference, the probability map generated by the U-Net was converted into a binary blood mask using a post-inference threshold of . After training, this threshold was selected from a threshold sweep performed on the validation subset using the trained U-Net outputs, as a compromise between precision and recall while maintaining stable Dice performance. Once this operating point was fixed, the final segmentation metrics were computed on the held-out test subset. The same threshold was also kept fixed for the qualitative visualizations and the online in vitro robotic experiments with artificial fluid. Connected-component analysis was subsequently applied to extract the blood regions and compute the descriptors required by the task planner.
The performance of the segmentation model was evaluated using standard metrics in medical image analysis, including the Dice coefficient, Intersection over Union (IoU), precision, and recall. Since the model outputs a pixel-wise probability map, different binarization thresholds were analyzed on the validation subset to select the operating point used for inference.
In addition, an error-specific analysis was performed by computing pixel-level true positives (TP), false positives (FP), false negatives (FN), and true negatives (TN). From these values, the false discovery rate (FDR = FP/(TP + FP)) and false negative rate (FNR = FN/(TP + FN)) were computed to explicitly quantify over-segmentation and missed bleeding pixels, respectively. Moreover, a preliminary robustness analysis was conducted by introducing controlled visual perturbations to the test images, including Gaussian blur, synthetic specular highlights, partial occlusions, and smoke-like degradations. The objective of this analysis was to evaluate the sensitivity of the perception module to challenging visual conditions commonly encountered in minimally invasive surgery.
Because the segmentation output is used by the robotic pipeline to define the navigation target, a task-oriented geometric analysis was also performed. In particular, the centroid displacement was computed as the Euclidean distance between the centroid of the selected predicted target region and the centroid of the corresponding ground-truth bleeding region. This metric was used to estimate the potential propagation of segmentation errors to the target localization stage of the navigation module. Additionally, missed-target cases and false-target cases were analyzed to evaluate situations where the perception module failed to detect a valid bleeding target or generated an incorrect target region.
2.5.2. Robotic Aspirator Evaluation
The performance and robustness of the autonomous robotic aspirator have been evaluated under three distinct bleeding scenarios (see Figure 7). These scenarios, designed to emulate representative intraoperative conditions, were defined based on the relative position between the bleeding source and the resulting blood accumulation, which is influenced by gravity and the surface inclination of the bleeding container:
Figure 7.
Bleeding scenarios simulated during the experimentation: (a) Source-centered accumulation (S1); (b) Downstream flow accumulation (S2); and (c) Bilateral flow distribution (S3). The bleeding source is represented with a green circle.
- Source-centered accumulation (S1): the inclination of the blood container is such that blood remains localized in close proximity to the bleeding source. This condition represents a flat or near-horizontal surgical field where gravitational effects are minimal, allowing blood to pool around the origin of bleeding.
- Downstream flow accumulation (S2): the blood container is inclined such that blood flows away from the bleeding source, accumulating at a distal location. This scenario mimics surgical conditions where the patient’s anatomy or positioning introduces a slope, such as in laparoscopic procedures or surgeries involving angled anatomical structures, where fluids tend to migrate due to gravity.
- Bilateral flow distribution (S3): in this case, the bleeding source is positioned such that blood spreads semi-symmetrically to both sides of the source, creating multiple accumulation regions, leading to a more complex spatial distribution of blood. This situation reflects cases where anatomical features or tissue geometries cause blood to bifurcate, such as around raised structures, cavities, or during procedures with uneven surfaces where fluid disperses in multiple directions.
For each bleeding scenario, four different suction strategies were implemented and compared, namely: geometric centroid (C1), source-oriented centroid (C2), front-oriented centroid (C3), and deepest-point target (C4). These strategies differ in the method used to compute the centroid of the detected blood region ( in Figure 4), which directly determines the target position of the suction tool. Let B denote the set of pixels belonging to the bleeding region, with cardinality . Let denote the image-plane coordinates of each pixel , and let denote the 2D target point. The computation of for each suction strategy is performed as follows:
- Geometric centroid (C1): This method provides a global estimate of the spatial distribution of the bleeding region. The centroid is computed as:
- Source-oriented centroid (C2): This strategy exploits the temporal persistence map to prioritize pixels in the vicinity of the bleeding source. Let denote the subset of persistent pixels:where denotes the p-th percentile of persistence values within the bleeding region ( in our implementation). The centroid is then computed as:
- Front-oriented centroid (C3): In contrast to the previous strategy, this method prioritizes pixels with lower persistence, which are assumed to correspond to the advancing bleeding front. Each pixel is assigned a weight inversely proportional to its persistence value:The weighted centroid is then computed as:
- Deepest-point target (C4): This strategy selects the most interior point of the bleeding region by exploiting the distance transform of the segmented mask. Let denote the distance from pixel to the nearest boundary of the bleeding region. The target index is defined as:The corresponding image-plane coordinates are then given by
Figure 8 illustrates the temporal evolution of the target position computation using the four centroid-based methods as the bleeding region progressively expands. This comparison highlights the distinct behaviors of the proposed strategies under dynamic conditions. From left to right, the sequence shows how each method responds to changes in the spatial distribution of blood over time. The geometric centroid (C1) remains centered within the overall bleeding region, providing a global representation of its distribution. The source-oriented centroid (C2) focuses on areas with sustained bleeding, remaining close to the bleeding source. In contrast, the front-oriented centroid (C3) shifts toward newly emerging regions, following the expansion of the bleeding front. Finally, the deepest-point target (C4) consistently identifies the most interior region of the accumulated blood, avoiding situations in which the estimated target falls outside the active bleeding flow, as may occur with other methods.
Figure 8.
Temporal evolution of the four centroid-based methods to compute the suction target position. From left to right, the images show the expansion of the bleeding region over time. The colored markers indicate the target positions computed from this detected mask by each centroid-based strategy: C1 (cyan), C2 (yellow), C3 (green), and C4 (magenta). From left to right, the sequence shows how the detected blood region and the resulting target candidates evolve as the artificial fluid spreads over time.
For each suction strategy, 20 independent trials were conducted in each bleeding scenario, with a trial defined as a single experimental run, beginning with the manual injection of approximately 10 mL of artificial blood and ending when the suction process is completed. In addition to the four autonomous centroid-based strategies, a manual aspiration (M) baseline was also evaluated for comparison purposes. Considering the five strategies evaluated and three scenarios, a total of 300 trials were conducted, corresponding to 100 trials per scenario (see Table 1).
Table 1.
Summary of experimental trials per bleeding scenario and centroid strategy.
This design enables a comprehensive assessment of how centroid estimation methods perform under varying fluid dynamics and spatial distributions, which are critical factors in real surgical environments.
To quantitatively assess the performance of the proposed system, the following metrics were computed for each trial:
- System response time (s): elapsed time between the detection of a valid bleeding region and the generation of the corresponding navigation command. Therefore, it quantifies the computational latency of the autonomous pipeline.
- Suction efficiency (pixels/s): defined as the ratio between the removed bleeding area and the suction time, providing a measure of the amount of blood removed per unit time.
- Removed area (%): represents the percentage of blood that was successfully removed upon completion of the suction process.
To further analyze the differences between the centroid-based strategies, an additional geometric metric was defined to quantify the spatial discrepancy between target positions. Let denote the 2D coordinates of the centroid obtained with strategy . The pairwise distance between centroids i and j is defined as:
This metric provides a quantitative measure of the spatial variability between centroid-based strategies. For each bleeding scenario, the reported distances correspond to the mean values computed over the 80 trials performed under that scenario.
2.5.3. Statistical Analysis
To evaluate whether the differences observed between centroid-based strategies were statistically significant, a non-parametric statistical analysis was performed for each bleeding scenario and evaluation metric. Since normality could not be assumed for all distributions, Kruskal–Wallis tests were used to assess global differences among strategies. When significant differences were detected (), post hoc pairwise comparisons were conducted using Dunn’s test with Holm correction for multiple comparisons.
2.5.4. Obstacle Avoidance Evaluation
To evaluate the obstacle-avoidance behavior of the proposed APF-based navigation framework, additional experimental trials were conducted under controlled laboratory conditions. Three conditions were considered: no obstacle, static obstacle, and moving obstacle. The no-obstacle condition was used as a reference for nominal target convergence. In the static-obstacle condition, an obstacle tool was introduced between the robotic aspirator and the target bleeding region to evaluate the planner response in the presence of a fixed obstacle. In the moving-obstacle condition, an obstacle tool was manually displaced during execution to emulate dynamic changes in the surgical workspace and assess the reactive behavior of the navigation system under time-varying conditions.
The evaluation metrics were target-reaching success, final positioning error, and minimum modeled physical clearance between the aspirator and the obstacle tool. Target-reaching success was defined as the percentage of trials in which the aspirator reached the target position. Final positioning error was defined as the Euclidean distance between the aspirator tip and the target at the end of the trial. Minimum modeled physical clearance was defined as the minimum distance between the external surfaces of the aspirator and obstacle tools during each trial.
3. Results
3.1. Blood Segmentation Results
The pixel-wise performance of the blood segmentation model was evaluated on the held-out test subset of the annotated gynecological surgical-image dataset. This subset was not used for model training or threshold selection. These results quantify the behavior of the U-Net in the surgical-image domain.In terms of pixel-wise prediction accuracy, the network achieved values of 98.9% and 98.1% on the validation and test subsets, respectively, indicating a reliable distinction between bleeding and non-bleeding regions. This metric is reported only for completeness and was not used as the main indicator of segmentation performance due to the strong class imbalance between bleeding and background pixels. In the evaluated test subset, bleeding pixels represented approximately 3.3% of all pixels; therefore, Dice, IoU, precision, recall, FDR, and FNR are considered more informative for assessing segmentation performance.
To further analyze the segmentation performance, the influence of the binarization threshold was evaluated. As shown in Figure 9, the Dice coefficient remains stable within the range . Although the maximum Dice value is achieved at , a threshold of was selected as it provides a better balance between precision and recall while maintaining comparable segmentation performance.
Figure 9.
Dice coefficient versus segmentation threshold , showing stable performance in the selected range.
The quantitative results obtained on the test dataset show that the model achieved a Dice coefficient of 0.686 and an IoU of 0.565, with precision and recall values of 0.72 and 0.73, respectively. These values indicate moderate pixel-wise segmentation performance, which is sufficient to extract approximate bleeding-region locations in many cases but also reflects non-negligible segmentation errors that may affect target localization. During training, the Binary Cross-Entropy loss decreased steadily for both training and validation subsets. The absence of divergence between the training and validation loss curves suggested stable convergence without clear evidence of severe overfitting.
Qualitative examples of the segmentation results are shown in Figure 10. The model generally identifies the main bleeding regions under variations in illumination, tissue appearance, and the presence of surgical instruments, although boundary inaccuracies, false positives, and missed pixels can occur. These qualitative results should therefore be interpreted together with the error-specific and task-oriented analyses reported below. In addition to the quantitative evaluation, a representative visualization of the perception layer operating on real surgical images is provided in the accompanying multimedia material. The video illustrates the real-time performance of the blood segmentation module, where the predicted blood mask and the geometric centroid of each region are overlaid onto the endoscopic image.
Figure 10.
Qualitative bleeding segmentation results on representative test images. (a–d) Each subfigure shows the original endoscopic frame (left) and the corresponding predicted blood mask (right).
To assess the impact of segmentation errors on the robotic pipeline, an error-specific and task-oriented evaluation was conducted. Table 2 summarizes the obtained results in terms of false detections, missed bleeding regions, and target localization accuracy. The error-specific analysis yielded a false discovery rate of 0.231 and a false negative rate of 0.223, indicating moderate levels of both over-segmentation and missed bleeding pixels. From a task-oriented perspective, the median centroid displacement between predicted and ground-truth target regions was 7.47 pixels (approximately 2.9% of the image width), suggesting that, in most cases, the estimated navigation target remained spatially close to the expected bleeding location despite segmentation inaccuracies. However, missed-target and false-target cases were also observed, indicating that perception failures may affect the robustness of the target localization stage of the autonomous robotic pipeline. Nevertheless, under the controlled experimental conditions considered in this work, the perception module provided sufficiently stable target estimations to enable autonomous blood aspiration during the robotic experiments.
Table 2.
Error-specific and task-oriented evaluation of the blood segmentation module.
Finally, a preliminary robustness analysis of the perception module was conducted by introducing controlled perturbations to the input images, including Gaussian blur, synthetic specular highlights, partial occlusions, and smoke-like degradations. This analysis was intended as an exploratory sensitivity assessment of the segmentation model under challenging visual conditions and does not replace validation under real surgical environments. The robustness analysis showed that moderate visual degradations such as blur, specular highlights, and partial occlusions produced only limited reductions in segmentation performance and target localization accuracy. In contrast, smoke-like degradations substantially affected the perception module, leading to lower Dice scores, larger centroid deviations, and a significant increase in missed-target cases, Table 3.
Table 3.
Preliminary robustness analysis of the blood segmentation module under controlled visual perturbations.
In this offline robustness analysis, the smoke/haze condition should be interpreted as the most critical visual perturbation for the current perception module. Compared with the original test images, this condition produced the largest reduction in Dice score and the highest increase in missed-target cases, indicating that severe visibility degradation can directly affect both blood-mask segmentation and target localization.
3.2. Robotic Aspirator Performance
This section presents the experimental results obtained for the evaluation of the autonomous robotic aspirator. First, a geometric analysis of the centroid-based strategies is provided to assess the spatial differences between target positions. Then, the overall system performance is evaluated using quantitative metrics. Finally, the variability of the results is analyzed through distribution-based representations.
A complementary video is provided to qualitatively illustrate the performance of the complete system. The first part of the video presents the system behavior in a single bleeding source scenario, followed by an experiment with multiple bleeding sources, demonstrating the capability of the autonomous robotic aspirator to detect, prioritize, and remove multiple blood regions. For each experiment, both an external view of the full robotic setup and the real-time visualization delivered to the HRI interface are shown, enabling a comprehensive understanding of the system operation from both perspectives. Finally, the temporal evolution of the centroids computed using the four suction strategies is shown for a representative bleeding scenario as the blood flows and accumulates. This visualization highlights the distinct target selection behaviors of each method and their influence on the resulting navigation of the robotic aspirator.
3.2.1. Geometric Analysis of Centroid Strategies
Table 4 reports the average pairwise distances between centroid-based strategies for each bleeding scenario. The results show that the centroid strategies produce distinct target locations, with varying levels of spatial separation depending on the bleeding scenario. In all cases, non-zero distances are observed between strategies, confirming that each method leads to different navigation targets. However, results reveal that strategies and lead to similar results in all bleeding scenarios evaluated. Larger distances are observed between certain pairs of strategies, which will be discussed in the following section.
Table 4.
Average pairwise centroid distances (pixels) for each bleeding scenario (mean over 80 trials).
3.2.2. Quantitative Performance Evaluation
Table 5 presents the average values of the performance metrics, computed over the 80 trials conducted for each bleeding scenario, as defined in Section 2.5.2. The system response time and removed area provide an overall indication of the system effectiveness, reflecting the computational latency of the autonomous pipeline and the capability to remove the bleeding region. In contrast, suction efficiency is used to compare the performance of the four suction strategies across different scenarios. System response time was not considered for manual aspiration, since it would mainly correspond to the operator’s unmeasurable visual-motor response rather than to an autonomous system processing delay.
Table 5.
Comparison of the system performance for the evaluated bleeding scenarios using the four centroid-based suction strategies (C1–C4) and manual aspiration (M).
The results show that all strategies achieve consistently low system response times, with values below 0.04 s in all scenarios, indicating fast system response regardless of the selected method. Additionally, all strategies achieve a high removed area, with values ranging approximately from 80% to 94% across the evaluated scenarios, demonstrating the capability of the system to effectively remove the bleeding regions. It should be noted that full (100%) removal is not achieved, as the suction process is intentionally stopped when the remaining area falls below a predefined threshold pixels in the implemented algorithm, in order to avoid unnecessary tool motion and reduce oscillatory behavior around small residual regions.
In the source-centered accumulation scenario (S1), the highest efficiency value is obtained with strategies and , while and exhibit longer execution times and lower efficiency. However, and achieve higher removed area percentages. In the downstream flow accumulation scenario (S2), larger differences between strategies are observed. Strategy achieves the highest efficiency, whereas and present significantly longer execution times and lower efficiency values. In the bilateral flow distribution scenario (S3), performance variability increases across strategies. Strategy achieves the highest efficiency, while , , and exhibit longer execution times. In terms of removed area, all strategies achieve high removal percentages, with and obtaining the highest values.
The manual aspiration baseline achieved high removed-area values across all evaluated scenarios, while also obtaining the highest suction efficiency values. These results provide a preliminary reference to contextualize the performance of the autonomous strategies under controlled laboratory conditions. In particular, strategies (S1), (S2), and (S3) achieved the closest performance to manual aspiration in terms of suction efficiency.
To further evaluate whether the observed differences between centroid-based strategies were statistically significant, a non-parametric statistical analysis was conducted for each bleeding scenario and evaluation metric. Table 6 summarizes the results of the statistical analysis.
Table 6.
Results of the statistical analysis for the four centroid-based suction strategies across the evaluated bleeding scenarios. Global differences were assessed using Kruskal–Wallis tests, followed by Dunn post hoc comparisons with Holm correction when significant differences were detected.
The statistical analysis revealed significant differences between centroid-based strategies for removed area and suction efficiency in scenarios S1 and S2. In contrast, no statistically significant differences were observed for any metric in scenario S3. Post hoc analysis showed that, in S1, strategy achieved significantly higher suction efficiency compared with several other strategies, whereas and obtained significantly higher removed area values. In S2, significant differences were mainly observed between and strategies and , particularly for suction efficiency.
3.2.3. Distribution Analysis of Performance Metrics
Figure 11 and Figure 12 present the distribution of removed area (%) and suction efficiency (pixels/s), respectively, for the four centroid-based strategies across the three bleeding scenarios. Overall, the boxplots highlight differences in variability between centroid-based strategies, which are not fully captured by the average values reported in Table 5.
Figure 11.
Comparative results of the removed area for the four suction strategies and for the three bleeding scenarios: (a) Bleeding scenario 1, (b) Bleeding scenario 2, and (c) Bleeding scenario 3.
Figure 12.
Comparative results of the suction efficiency (pixels/s) for the four suction strategies and for the three bleeding scenarios: (a) Bleeding scenario 1, (b) Bleeding scenario 2, and (c) Bleeding scenario 3.
Regarding the removed area, the distributions show generally high values for all strategies, with median values above 85% in most cases. In scenario S1, strategies and exhibit more concentrated distributions around higher values, whereas and present a wider spread. In scenario S2, all strategies show relatively compact distributions, although some outliers with lower removed area are observed, particularly for . In scenario S3, all strategies achieve high median values, with increased variability in .
For suction efficiency, greater variability is observed across both strategies and scenarios. In scenario S1, presents the highest median efficiency with relatively low dispersion, while shows lower median values and higher variability. In scenario S2, achieves the highest efficiency values with a broader distribution. In scenario S3, the efficiency distributions are more dispersed across all strategies, with showing higher median values compared with the others.
3.2.4. Obstacle Avoidance Results
The obstacle-avoidance results are presented through aggregated metrics and representative trajectory examples. Table 7 summarizes the quantitative results, whereas Figure 13 and Figure 14 illustrate representative static- and moving-obstacle trials.
Table 7.
Obstacle-avoidance evaluation under no-obstacle, static-obstacle, and moving-obstacle conditions. Continuous metrics are reported as mean ± standard deviation over the experimental trials.
Figure 13.
Example of the APF-based trajectory generated in the presence of a static obstacle. The blue shaded region represents the modeled safety envelope around the obstacle.The repulsive component of the APF modifies the aspirator trajectory to avoid the obstacle while maintaining convergence toward the target position.
Figure 14.
Temporal evolution of the APF-based obstacle avoidance response under static and moving obstacle conditions. (Top row): distance between the robot tool tip and the obstacle over time, compared with the obstacle influence radius . The green region indicates distances outside the obstacle influence area, the yellow region indicates the repulsive-field activation zone, and the red region indicates collision-risk distances. (Bottom row): obstacle velocity profile. (a) Static obstacle experiment, showing smooth repulsive behavior and recovery outside the obstacle influence region. (b) Moving obstacle experiment, illustrating the reactive adaptation of the APF-based planner to dynamic obstacle motion while maintaining collision avoidance.
The target was reached in all experimental trials under the evaluated conditions, with final positioning errors close to 2 mm on average. When obstacles were introduced, the minimum distance to obstacle decreased, especially in the moving-obstacle condition, where the obstacle tool was manually displaced and its motion was independent from the APF controller of the aspirator. However, the minimum modeled clearance remained positive in all experimental trials, indicating that no modeled physical contact occurred.
Figure 13 illustrates an example of the three-dimensional trajectory generated in the presence of a static obstacle. The repulsive component of the APF deformed the nominal trajectory of the robotic aspirator, allowing the system to avoid the obstacle safety envelope while maintaining convergence toward the target position. The final target positioning error remained below 1 mm in the evaluated experiment.
Figure 14 shows the temporal evolution of the APF response under static (a) and moving obstacle conditions (b). The top row illustrates the distance between the robotic tool tip and the obstacle over time, compared with the obstacle influence radius . The obstacle position reference is also represented. The green region indicates safe distances outside the obstacle influence area, the yellow region corresponds to the obstacle influence zone where repulsive interactions become active, and the red region represents collision-risk distances. The bottom row shows the obstacle velocity during the experiments, which was included to facilitate the interpretation of the relative motion between the obstacle and the robotic aspirator.
In the static case, the repulsive interaction increased the separation distance once the robotic aspirator approached the obstacle influence region, generating a smooth collision-free trajectory. In the moving-obstacle experiment, the navigation framework continuously adapted the trajectory according to the obstacle motion, producing reactive avoidance behavior while preserving stable convergence toward the target region. The peak observed around 70 s corresponds to the instant at which the obstacle actively approaches the robotic aspirator. As can be observed, the navigation framework reacts appropriately to this situation by increasing the separation distance and maintaining collision-free behavior.
These experiments demonstrate that the implemented APF framework incorporates both attractive and repulsive field components and is capable of handling obstacle avoidance under controlled laboratory conditions. A video demonstrating the dynamic obstacle avoidance experiment has been included as Supplementary Materials.
4. Discussion
The results obtained in this work highlight the impact of the centroid estimation strategy on the performance of the autonomous robotic aspirator. Although all strategies achieve high removed area values and low system response times, the statistical analysis revealed significant differences in removed area, and efficiency depending on both the selected strategy and the bleeding scenario.
From the geometric analysis, the pairwise centroid distances reveal that different strategies generate distinct target positions, with consistent similarities observed between certain methods. In particular, strategies and exhibit the smallest spatial discrepancies across all scenarios, indicating similar target selection behavior. This geometric similarity does not directly translate into equivalent performance, as reflected in the quantitative results. This can be explained by the fact that the centroid distance captures a static spatial relationship, whereas the robotic aspirator operates in a dynamic environment.
The quantitative evaluation shows that no single centroid strategy provides optimal performance across all scenarios. In the source-centered accumulation scenario (S1), strategies that prioritize persistent or central regions, such as and , achieve higher efficiency. Statistical analysis confirmed significant differences between several centroid-based strategies for these metrics. In contrast, in the downstream flow scenario (S2), the deepest-point strategy () achieved the best average performance in terms of efficiency, although the statistical analysis did not reveal significant differences between strategies and . This suggests that, in scenarios with strong blood displacement, strategies that prioritize advanced or interior regions of the blood accumulation may improve the effectiveness of the suction process. For the bilateral flow scenario (S3), strategy achieved the highest average suction efficiency. However, no statistically significant differences were observed between centroid-based strategies in this scenario. This suggests that, under complex or multi-directional blood distributions, the effectiveness of the suction process becomes less dependent on the specific centroid computation method, highlighting the need for more adaptive or context-aware target selection strategies.
An important observation is the existence of a trade-off between suction efficiency and removed area. Strategies that achieve higher efficiency tend to remove a smaller percentage of the bleeding region, whereas strategies with longer execution times achieve higher removal percentages. This behavior suggests that faster strategies focus on the most relevant regions of the bleeding, while slower strategies continue operating on smaller residual areas, increasing the overall removal percentage.
The manual aspiration baseline provides a reference for contextualizing the autonomous strategies. While manual operation achieved the highest removed-area and suction-efficiency values, the autonomous results show that the main suction workflow can be completed by the robotic system under HRI supervision. This represents a change in task allocation, where the operator is no longer required to continuously command the suction motion, but supervises the autonomous execution and can intervene when necessary. From this perspective, the proposed framework increases autonomy in a repetitive supportive task and may contribute to reducing the operator workload associated with manual suction control.
The distribution analysis further reveals differences in robustness across strategies. While some methods achieve high average performance, their variability across trials can differ significantly. Strategies such as in S1 and in S2 exhibit both high efficiency and relatively low dispersion, indicating stable behavior. In contrast, increased variability is observed in more complex scenarios such as S3, where blood distribution is less structured and multiple accumulation regions exist. This highlights the importance of considering not only average performance but also consistency when evaluating autonomous robotic systems.
Overall, these results demonstrate that the optimal centroid strategy is scenario-dependent. This suggests that adaptive approaches, capable of selecting or combining centroid strategies based on the characteristics of the bleeding, could further improve system performance. Additionally, the observed relationship between spatial target selection and task efficiency reinforces the importance of integrating perception and control strategies in a unified framework for autonomous surgical assistance.
5. Conclusions
This paper presented the design and experimental validation of a supervised autonomous robotic aspirator for blood removal under in vitro experimental conditions for minimally invasive surgery. The proposed system integrates perception, decision-making, and control modules within a unified framework, enabling autonomous navigation and suction based on visual information extracted from endoscopic images.
The experimental results demonstrate that the system is capable of reliably detecting and removing blood regions, achieving high removed area values and fast system response times across all evaluated scenarios. The comparison of different suction strategies shows that the choice of the centroid computation method has a significant impact on the efficiency and execution time of the suction process. A key finding of this work is that no single centroid strategy provides optimal performance across all bleeding scenarios. Instead, the results reveal a scenario-dependent behavior, where different strategies perform better depending on the spatial distribution and dynamics of the bleeding. Additionally, a trade-off between suction efficiency and removed area has been identified, highlighting the balance between rapid intervention and complete blood removal.
These findings suggest that future work should focus on adaptive strategies capable of selecting or combining centroid estimation methods based on the current surgical context. Additional research may also explore the integration of more advanced perception models and the extension of the system to in vivo validation scenarios. Overall, the proposed system represents a step forward toward increasing autonomy in surgical assistance, contributing to a reduction in surgeon workload and the improvement of surgical workflow efficiency.
Although the proposed system demonstrated robust performance in controlled in vitro conditions, real surgical environments introduce additional challenges that were not explicitly addressed in this work. First, the experimental validation was conducted using simulated bleeding, which does not fully reproduce the complexity of real surgical environments. The artificial bleeding model employed in the experimental validation does not consider the rheological behavior of real blood, including viscosity variations, non-Newtonian effects, and clot formation. These factors may influence the fluid dynamics and aspiration behavior in real surgical environments and should be considered in future validations. Other factors such as tissue deformation, organ motion, occlusions caused by surgical instruments, and illumination variability may also affect both the perception and autonomous navigation performance. Therefore, future work will focus on improving the robustness and adaptability of the proposed framework under realistic intraoperative conditions, including more complex experimental environments and in vivo validation. The preliminary robustness analysis also revealed that the perception module is sensitive to severe visibility degradations, particularly smoke-like perturbations, which substantially increased missed-target cases and centroid deviations. This suggests that surgical smoke and other intraoperative visual artifacts may significantly affect the reliability of autonomous perception and should be explicitly addressed in future work. Moreover, the current setup relies on an external RGB-D camera for depth acquisition. Although this configuration was adopted for experimental validation under controlled laboratory conditions, depth information in a clinical minimally invasive surgery environment could be obtained from commercially available stereoscopic endoscopes.
Since the proposed system is continuously supervised through the HRI interface, the operator receives visual feedback, the blood-segmentation overlay, and system-state information during operation. This supervision allows the operator to switch from autonomous navigation to teleoperation through the haptic controller whenever the autonomous behavior is considered unreliable.
Second, the perception module relies on a pretrained segmentation model evaluated on a specific dataset, and its generalization to different surgical procedures or imaging conditions may require further validation. In addition, the segmentation dataset was split at the image level because patient and procedure identifiers were not available in the public dataset used in this work. Additionally, the current approach assumes reliable depth estimation, which may be affected by noise or sensor limitations in real scenarios. Finally, the navigation strategy is based on a deterministic centroid selection without incorporating predictive or adaptive mechanisms. As shown in the results, the performance of each centroid strategy is scenario-dependent, which suggests that a fixed strategy may not be optimal under all conditions. Thus, future work will investigate adaptive context-aware strategy selection mechanisms capable of identifying the current bleeding dynamics and automatically selecting the most suitable centroid-based navigation strategy according to the surgical scenario.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/electronics15122551/s1, Video S1: real-time bleeding segmentation and centroid computation during a gynecological surgical procedure; Video S2: validation of the APF-based obstacle avoidance navigation strategy; Video S3: performance of the robotic aspirator in experiments involving single and multiple bleeding sources, together with the temporal evolution of the target position computation using the four centroid-based methods.
Author Contributions
Conceptualization, I.R.-B.; methodology, I.R.-B., E.G.-R. and C.L.-C.; software, E.G.-R. and Á.G.-C.; validation, E.G.-R.; formal analysis, I.R.-B. and V.F.M.; writing—original draft preparation, I.R.-B. and E.G.-R.; writing—review and editing, I.R.-B. and I.G.-M.; funding acquisition, I.R.-B. and V.F.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research was funded by the Spanish Ministry of Science and Innovation under grant numbers PID2021-125050OA-I00 and PID2022-138206OB-C31.
Data Availability Statement
The code and multimedia material supporting the results of this study are publicly available at: https://github.com/SurgicalRoboticsUMA/autonomous_aspirator (accessed on 3 June 2026).
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Yang, G.Z.; Cambias, J.; Cleary, K.; Daimler, E.; Drake, J.; Dupont, P.E.; Hata, N.; Kazanzides, P.; Martel, S.; Patel, R.V.; et al. Medical robotics-Regulatory, ethical, and legal considerations for increasing levels of autonomy. Sci. Robot. 2017, 2, eaam8638. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Estebanez, B.; del Saz-Orozco, P.; García-Morales, I.; Muñoz, V.F. Interfaz multimodal para un asistente robótico quirúrgico: Uso de reconocimiento de maniobras quirúrgicas. Rev. Iberoam. Autom. Inform. Ind. RIAI 2011, 8, 24–34. [Google Scholar] [CrossRef] [Scilit]
- Stolzenburg, J.U.; Franz, T.; Kallidonis, P.; Minh, D.; Dietel, A.; Hicks, J.; Nicolaus, M.; Al-Aown, A.; Liatsikos, E. Comparison of the FreeHand® robotic camera holder with human assistants during endoscopic extraperitoneal radical prostatectomy. BJU Int. 2011, 107, 970–974. [Google Scholar] [CrossRef] [Scilit]
- Noonan, D.; Mylonas, G.; Shang, J.; Payne, C.; Darzi, A.; Yang, G.Z. Gaze contingent control for an articulated mechatronic laparoscope. In Proceedings of the 2010 3rd IEEE RAS & EMBS International Conference on Biomedical Robotics and Biomechatronics; IEEE: New York, NY, USA, 2010; pp. 759–764. [Google Scholar] [CrossRef] [Scilit]
- Laina, I.; Rieke, N.; Rupprecht, C.; Vizcaíno, J.P.; Eslami, A.; Tombari, F.; Navab, N. Concurrent segmentation and localization for tracking of surgical instruments. In Medical Image Computing and Computer-Assisted Intervention—MICCAI 2017, Proceedings of the 20th International Conference; Lecture Notes in Computer Science (including subseries Lecture Notes in Artificial Intelligence and Lecture Notes in Bioinformatics); Springer: Cham, Switzerland, 2017; Volume 10434, pp. 664–672. [Google Scholar] [CrossRef] [Scilit]
- Du, X.; Kurmann, T.; Chang, P.L.; Allan, M.; Ourselin, S.; Sznitman, R.; Kelly, J.D.; Stoyanov, D. Articulated multi-instrument 2-d pose estimation using fully convolutional networks. IEEE Trans. Med. Imaging 2018, 37, 1276–1287. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rivas-Blanco, I.; Lopez-Casado, C.; Perez-del Pulgar, C.J.; Garcia-Vacas, F.; Fraile, J.C.; Munoz, V.F. Smart Cable-Driven Camera Robotic Assistant. IEEE Trans. Hum.-Mach. Syst. 2018, 48, 183–196. [Google Scholar] [CrossRef] [Scilit]
- Attanasio, A.; Scaglioni, B.; Leonetti, M.; Frangi, A.F.; Cross, W.; Biyani, C.S.; Valdastri, P. Autonomous Tissue Retraction in Robotic Assisted Minimally Invasive Surgery—A Feasibility Study. IEEE Robot. Autom. Lett. 2020, 5, 6528–6535. [Google Scholar] [CrossRef] [Scilit]
- Nguyen, N.D.; Nguyen, T.; Nahavandi, S.; Bhatti, A.; Guest, G. Manipulating soft tissues by deep reinforcement learning for autonomous robotic surgery. In Proceedings of the SysCon 2019—13th Annual IEEE International Systems Conference, Proceedings; Institute of Electrical and Electronics Engineers Inc.: New York, NY, USA, 2019. [Google Scholar] [CrossRef] [Scilit]
- Seita, D.; Krishnan, S.; Fox, R.; McKinley, S.; Canny, J.; Goldberg, K. Fast and Reliable Autonomous Surgical Debridement with Cable-Driven Robots Using a Two-Phase Calibration Procedure. In Proceedings of the Proceedings—IEEE International Conference on Robotics and Automation; Institute of Electrical and Electronics Engineers Inc.: New York, NY, USA, 2018; pp. 6651–6658. [Google Scholar] [CrossRef] [Scilit]
- Shademan, A.; Decker, R.S.; Opfermann, J.D.; Leonard, S.; Krieger, A.; Kim, P.C. Supervised autonomous robotic soft tissue surgery. Sci. Transl. Med. 2016, 8, 337ra64. [Google Scholar] [CrossRef] [Scilit]
- Saeidi, H.; Opfermann, J.D.; Kam, M.; Wei, S.; Leonard, S.; Hsieh, M.H.; Kang, J.U.; Krieger, A. Autonomous robotic laparoscopic surgery for intestinal anastomosis. Sci. Robot. 2022, 7, eabj2908. [Google Scholar] [CrossRef] [Scilit]
- Mikada, T.; Kanno, T.; Kawase, T.; Miyazaki, T.; Kawashima, K. Suturing Support by Human Cooperative Robot Control Using Deep Learning. IEEE Access 2020, 8, 167739–167746. [Google Scholar] [CrossRef] [Scilit]
- Chow, D.L.; Newman, W. Improved knot-tying methods for autonomous robot surgery. In Proceedings of the 2013 IEEE International Conference on Automation Science and Engineering (CASE); IEEE: New York, NY, USA, 2013; pp. 461–465. [Google Scholar] [CrossRef] [Scilit]
- Barragan, J.A.; Yang, J.; Yu, D.; Wachs, J.P. A neurotechnological aid for semi-autonomous suction in robotic-assisted surgery. Sci. Rep. 2022, 12, 4504. [Google Scholar] [CrossRef] [Scilit]
- Richter, F.; Shen, S.; Liu, F.; Huang, J.; Funk, E.K.; Orosco, R.K.; Yip, M.C. Autonomous Robotic Suction to Clear the Surgical Field for Hemostasis Using Image-Based Blood Flow Detection. IEEE Robot. Autom. Lett. 2021, 6, 1383–1390. [Google Scholar] [CrossRef] [Scilit]
- Ou, Y.; Tavakoli, M. Learning Autonomous Surgical Irrigation and Suction With the da Vinci Research Kit Using Reinforcement Learning. IEEE Trans. Autom. Sci. Eng. 2025, 22, 16753–16767. [Google Scholar] [CrossRef] [Scilit]
- Garcia-Martinez, A.; Vicente-Samper, J.M.; Sabater-Navarro, J.M. Automatic detection of surgical haemorrhage using computer vision. Artif. Intell. Med. 2017, 78, 55–60. [Google Scholar] [CrossRef] [Scilit]
- Horita, K.; Hida, K.; Itatani, Y.; Fujita, H.; Hidaka, Y.; Yamamoto, G.; Ito, M.; Obama, K. Real-time detection of active bleeding in laparoscopic colectomy using artificial intelligence. Surg. Endosc. 2024, 38, 3461–3469. [Google Scholar] [CrossRef] [Scilit]
- Hua, S.; Gao, J.; Wang, Z.; Yeerkenbieke, P.; Li, J.; Wang, J.; He, G.; Jiang, J.; Lu, Y.; Yu, Q.; et al. Automatic bleeding detection in laparoscopic surgery based on a faster region-based convolutional neural network. Ann. Transl. Med. 2022, 10, 546. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rabbani, N.; Seve, C.; Bourdel, N.; Bartoli, A. Video-based Computer-aided Laparoscopic Bleeding Management: A Space-time Memory Neural Network with Positional Encoding and Adversarial Domain Adaptation. Proc. Mach. Learn. Res. 2022, 172, 1–14. [Google Scholar]
- Richter, F.; Zhang, Y.; Zhi, Y.; Orosco, R.K.; Yip, M.C. Augmented reality predictive displays to help mitigate the effects of delayed telesurgery. In Proceedings of the IEEE International Conference on Robotics and Automation; IEEE: New York, NY, USA, 2019; pp. 444–450. [Google Scholar] [CrossRef] [Scilit]
- Lillicrap, T.P.; Hunt, J.J.; Pritzel, A.; Heess, N.; Erez, T.; Tassa, Y.; Silver, D.; Wierstra, D. Continuous control with deep reinforcement learning. arXiv 2015, arXiv:1509.02971. [Google Scholar] [CrossRef] [Scilit]
- Khatib, O. Real-time obstacle avoidance for manipulators and mobile robots. In Proceedings of the IEEE International Conference on Robotics and Automation; IEEE: New York, NY, USA, 1985; pp. 500–505. [Google Scholar] [CrossRef] [Scilit]
- Xia, X.; Li, T.; Sang, S.; Cheng, Y.; Ma, H.; Zhang, Q.; Yang, K. Path Planning for Obstacle Avoidance of Robot Arm Based on Improved Potential Field Method. Sensors 2023, 23, 3754. [Google Scholar] [CrossRef] [Scilit]
- Chen, Q.; Liu, Y.; Chen, Z.; Zhou, Y. An Autonomous Obstacle Avoidance Path Planning Method Involving PSO for Dual-Arm Surgical Robot. In Proceedings of the 2022 5th International Conference on Mechatronics, Robotics and Automation (ICMRA); IEEE: New York, NY, USA, 2022; pp. 1–6. [Google Scholar] [CrossRef] [Scilit]
- Surya Prakash, S.K.; Prajapati, D.; Narula, B.; Shukla, A. iAPF: An improved artificial potential field framework for asymmetric dual-arm manipulation with real-time inter-arm collision avoidance. Front. Robot. AI 2025, 12, 1604506. [Google Scholar] [CrossRef] [Scilit]
- Tang, A.; Cao, Q.; Pan, T. Spatial motion constraints for a minimally invasive surgical robot using customizable virtual fixtures. Int. J. Med. Robot. Comput. Assist. Surg. 2014, 10, 447–460. [Google Scholar] [CrossRef] [Scilit]
- Hao, L.; Liu, D.; Du, S.; Wang, Y.; Wu, B.; Wang, Q.; Zhang, N. An improved path planning algorithm based on artificial potential field and primal-dual neural network for surgical robot. Comput. Methods Programs Biomed. 2022, 227, 107202. [Google Scholar] [CrossRef] [Scilit]
- Góngora-Rodríguez, E.; Casado-Sánchez, N.; López-Casado, C.; Rivas Blanco, I. Consola de teleoperación de realidad mixta para sistemas quirúrgicos robóticos. Jornadas Autom. 2025, 46, 3045–4093. [Google Scholar] [CrossRef] [Scilit]
- Ronneberger, O.; Fischer, P.; Brox, T. U-Net: Convolutional Networks for Biomedical Image Segmentation. In Medical Image Computing and Computer-Assisted Intervention—MICCAI 2015, Proceedings of the 18th International Conference; Navab, N., Hornegger, J., Wells, W.M., Frangi, A.F., Eds.; Springer: Cham, Switzerland, 2015; pp. 234–241. [Google Scholar]
- Galan-Cuenca, A.; De Luis-Moura, D.; Herrera-Lopez, J.M.; Rollon, M.; Garcia-Morales, I.; Muñoz, V.F. Sutura automatizada para una plataforma robotica de asistencia a la cirugia laparoscopica. Rev. Iberoam. Autom. Inform. Ind. 2024, 21, 339–350. [Google Scholar] [CrossRef] [Scilit]
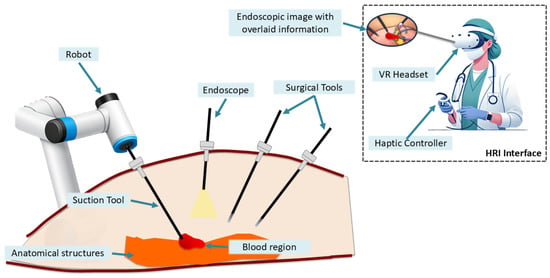
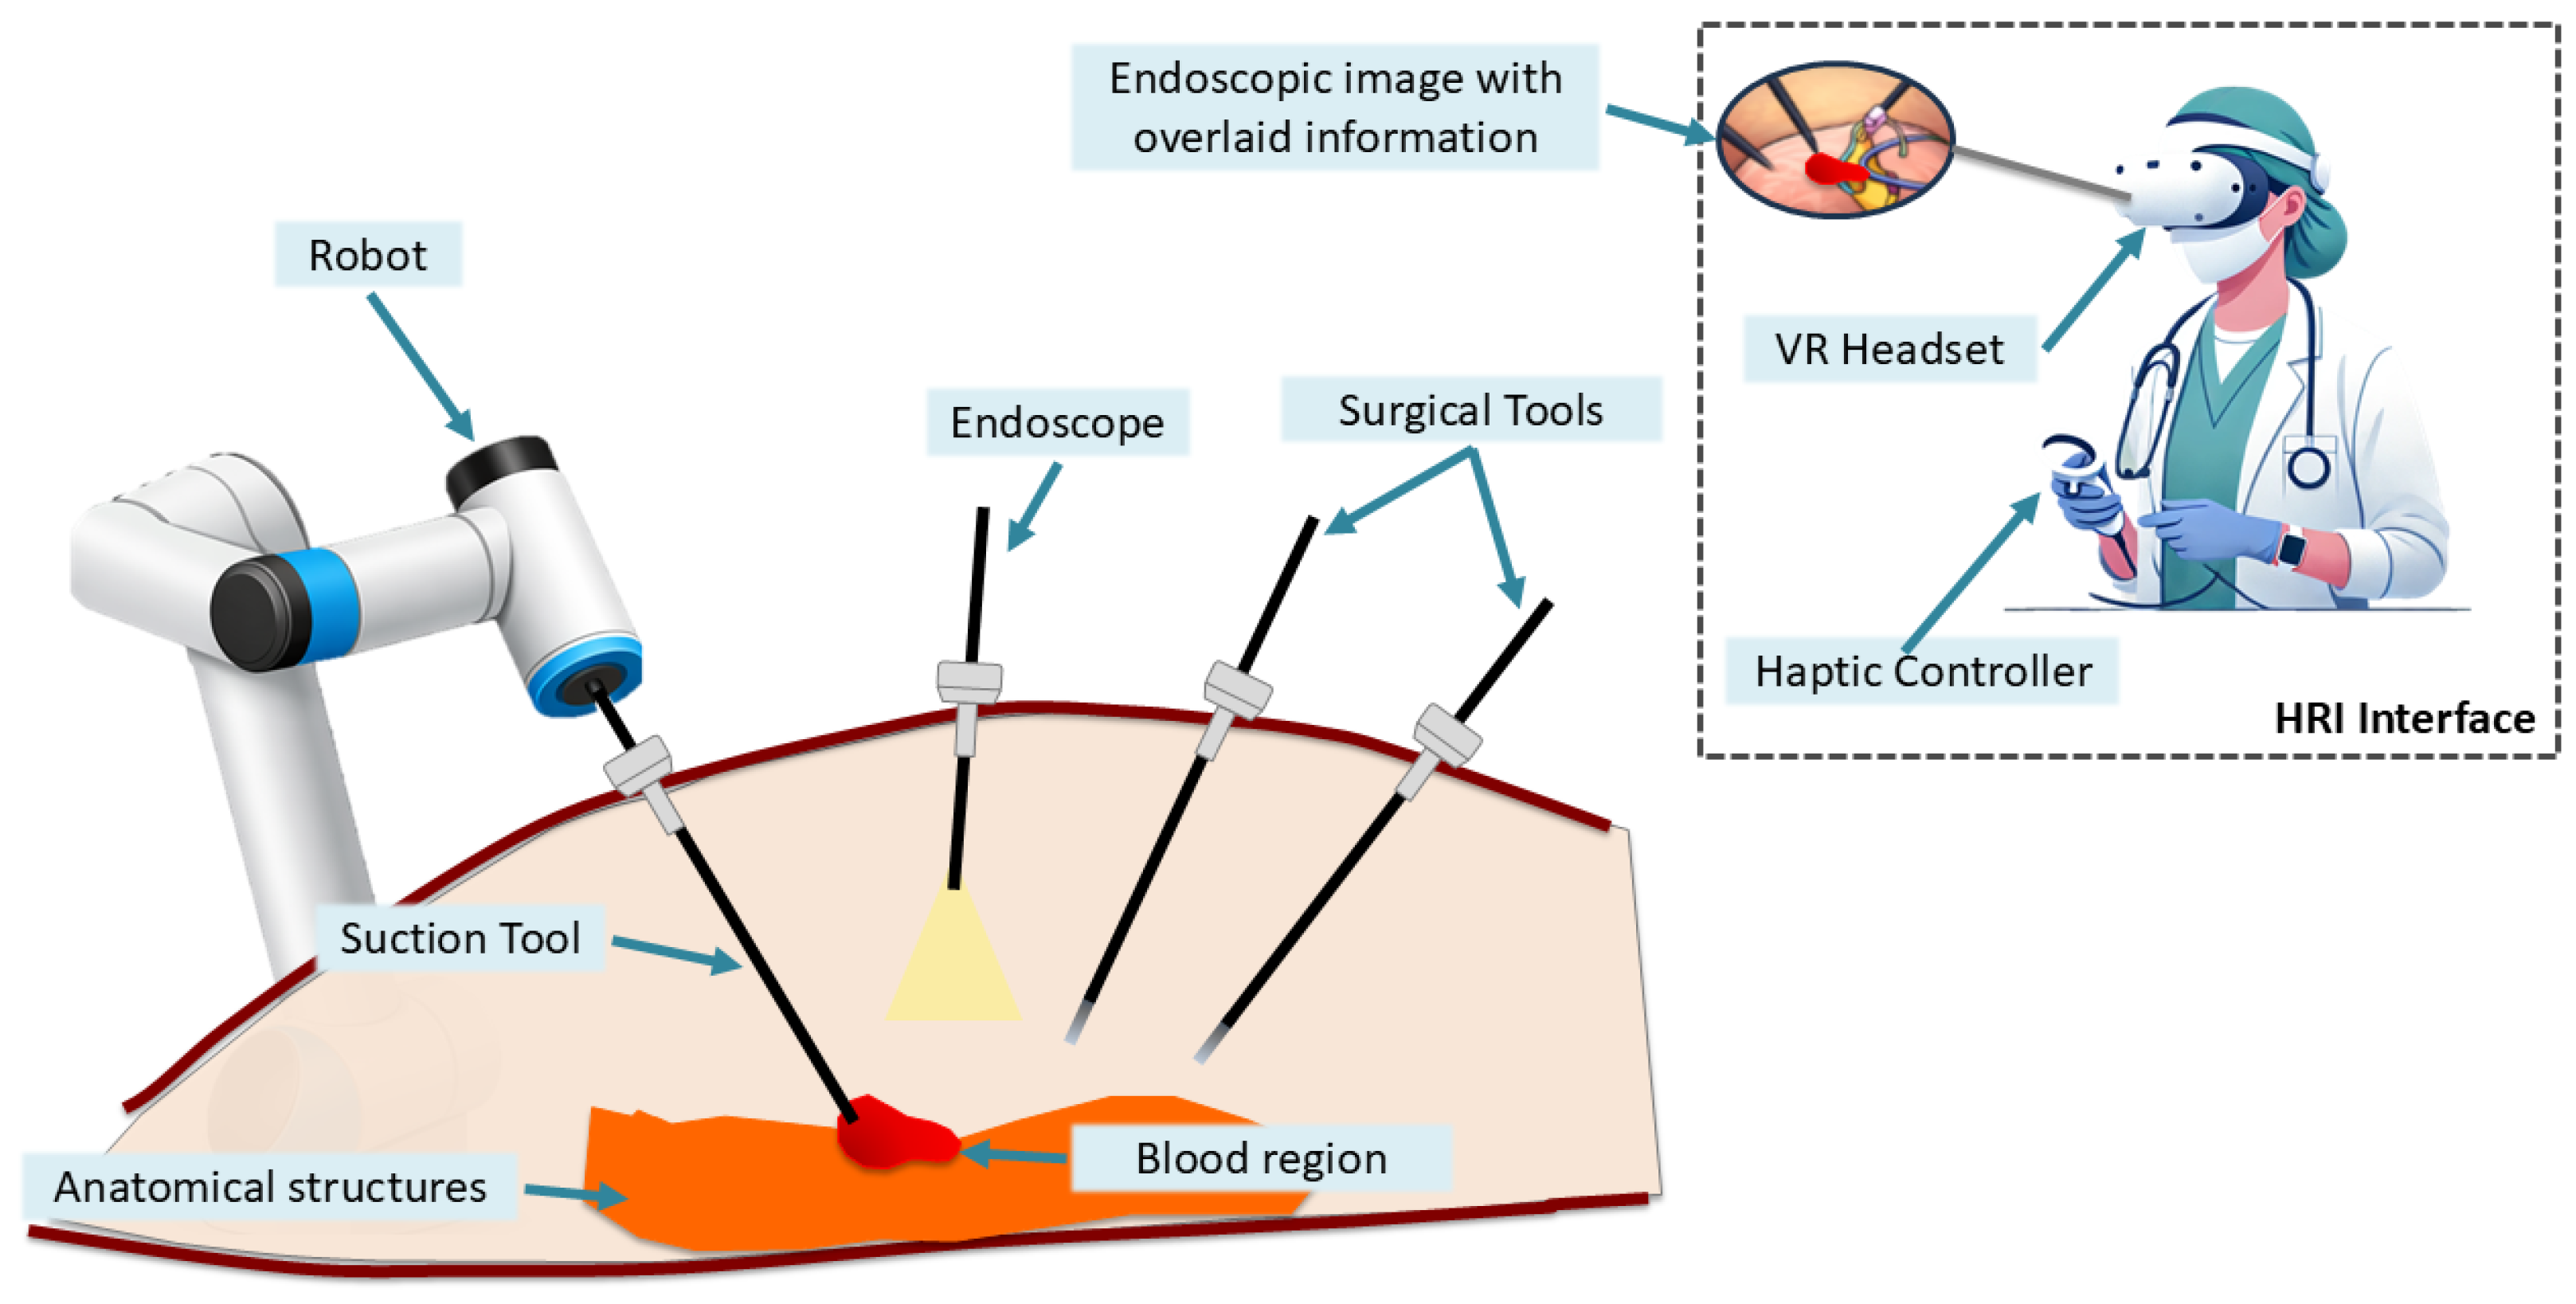
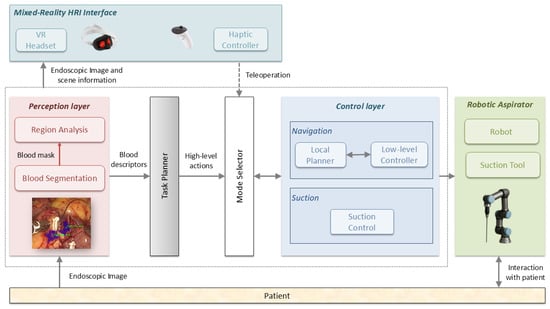
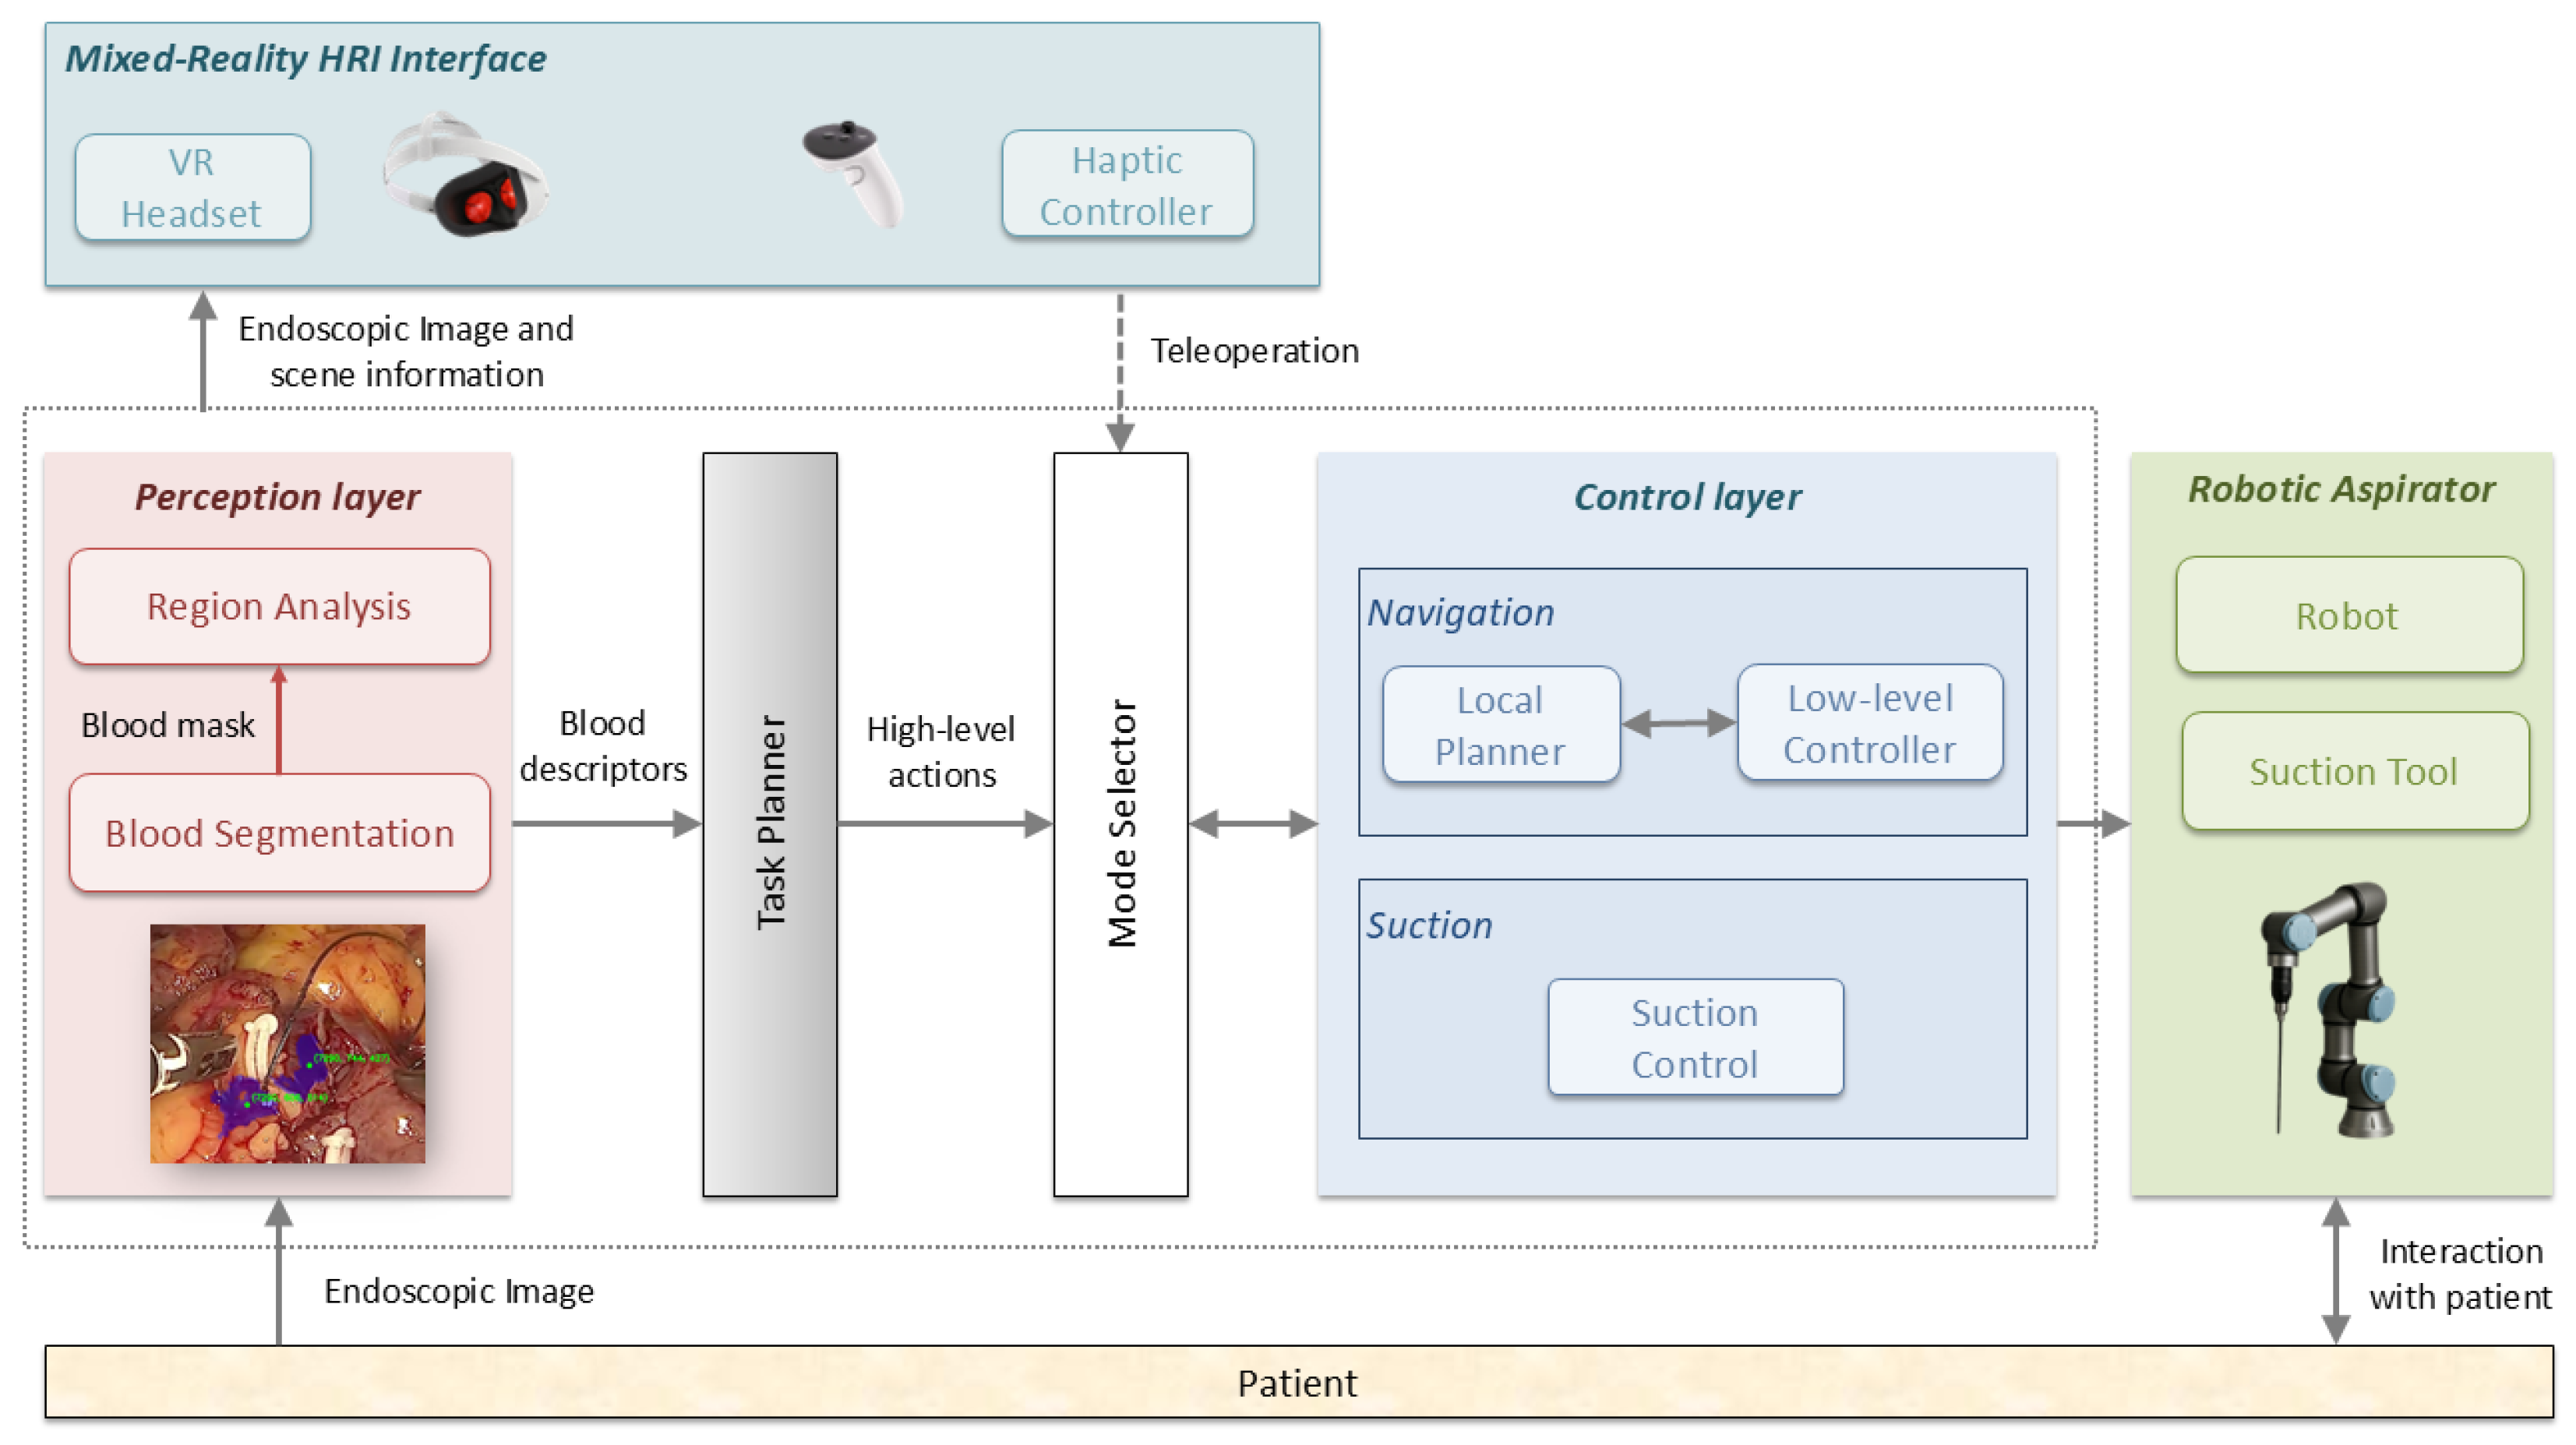
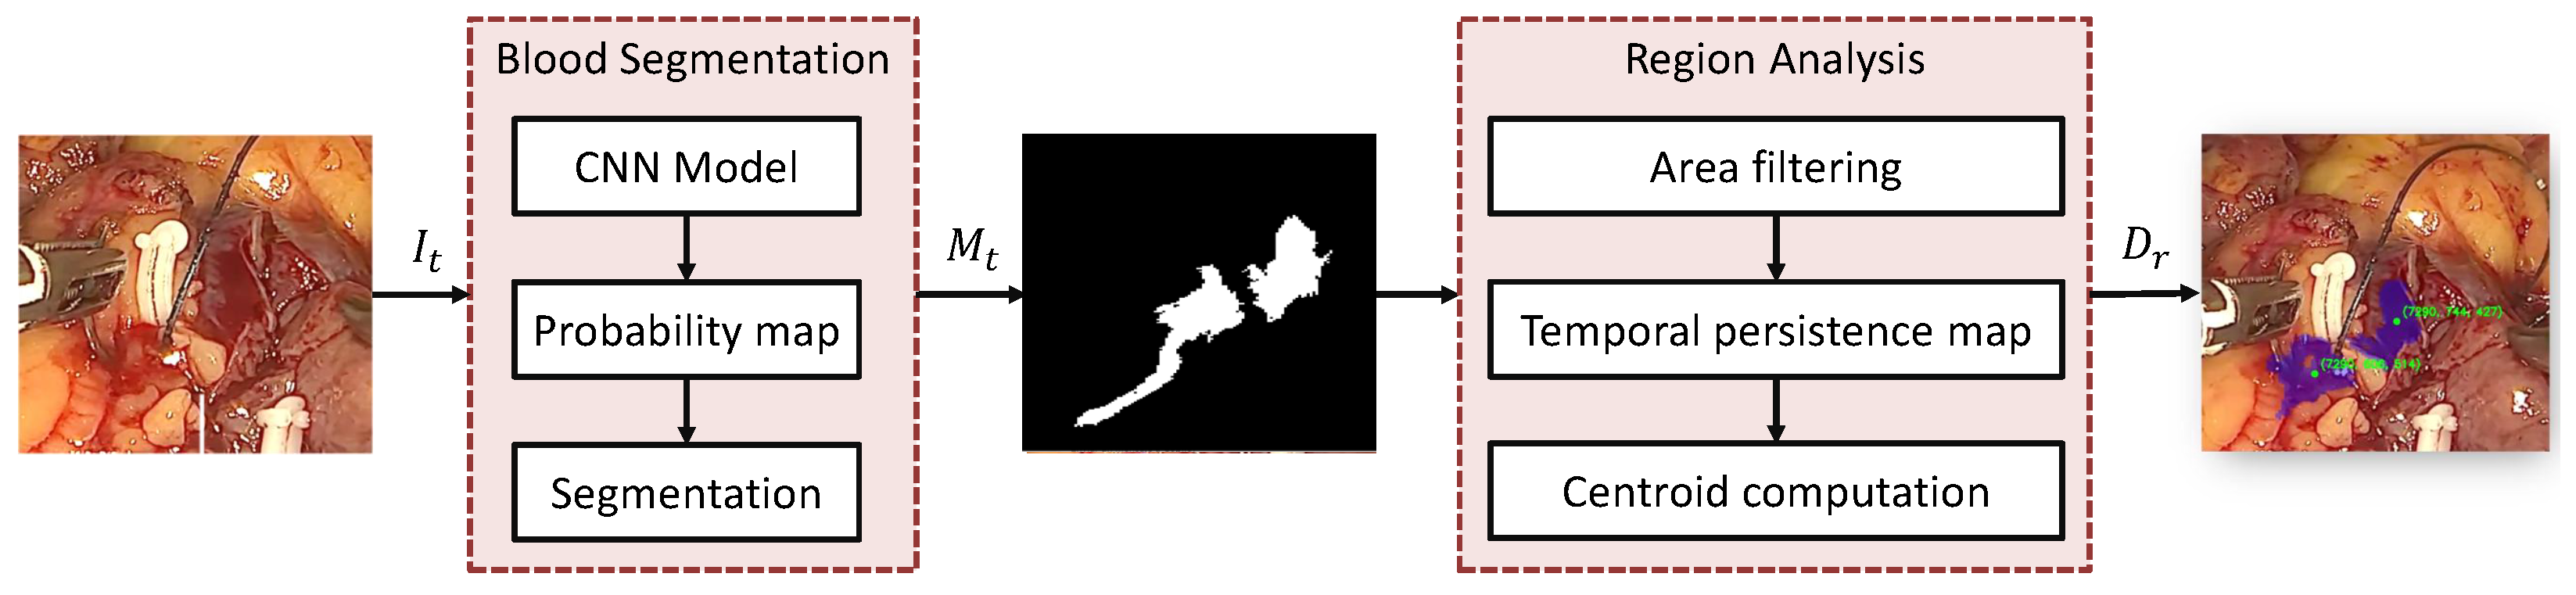
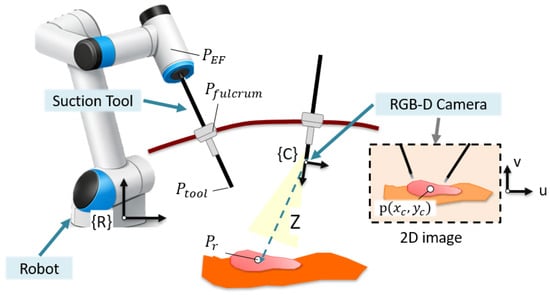
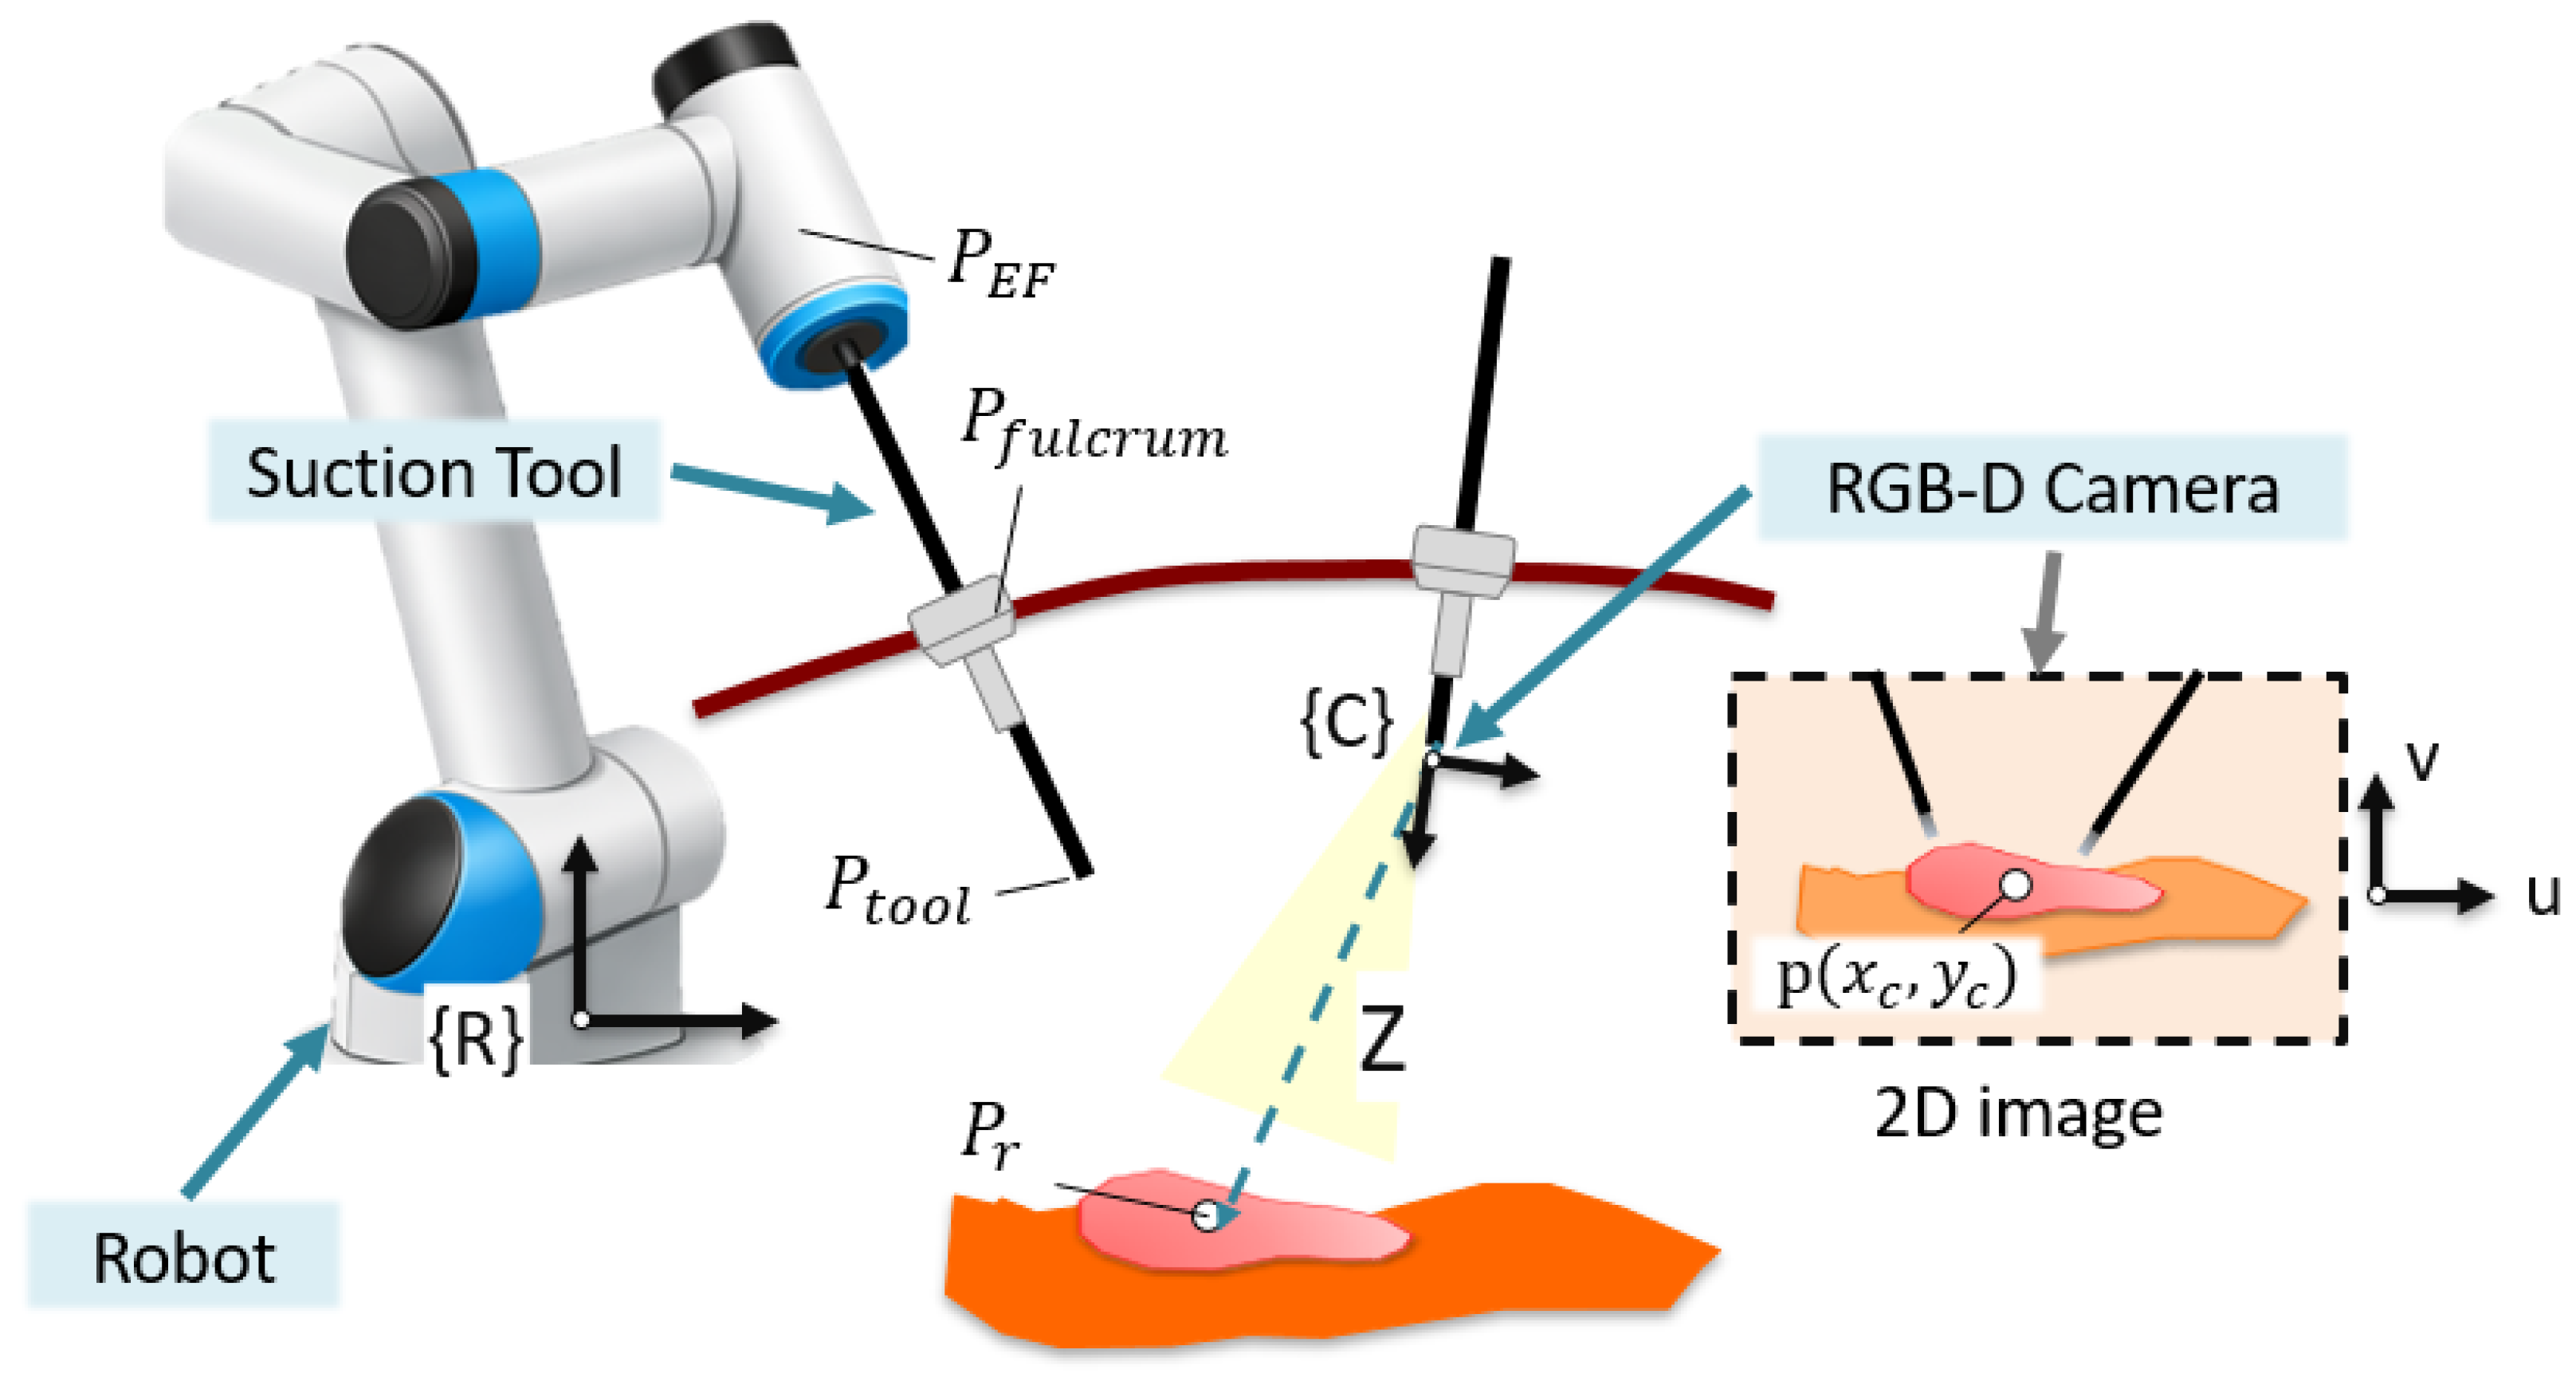
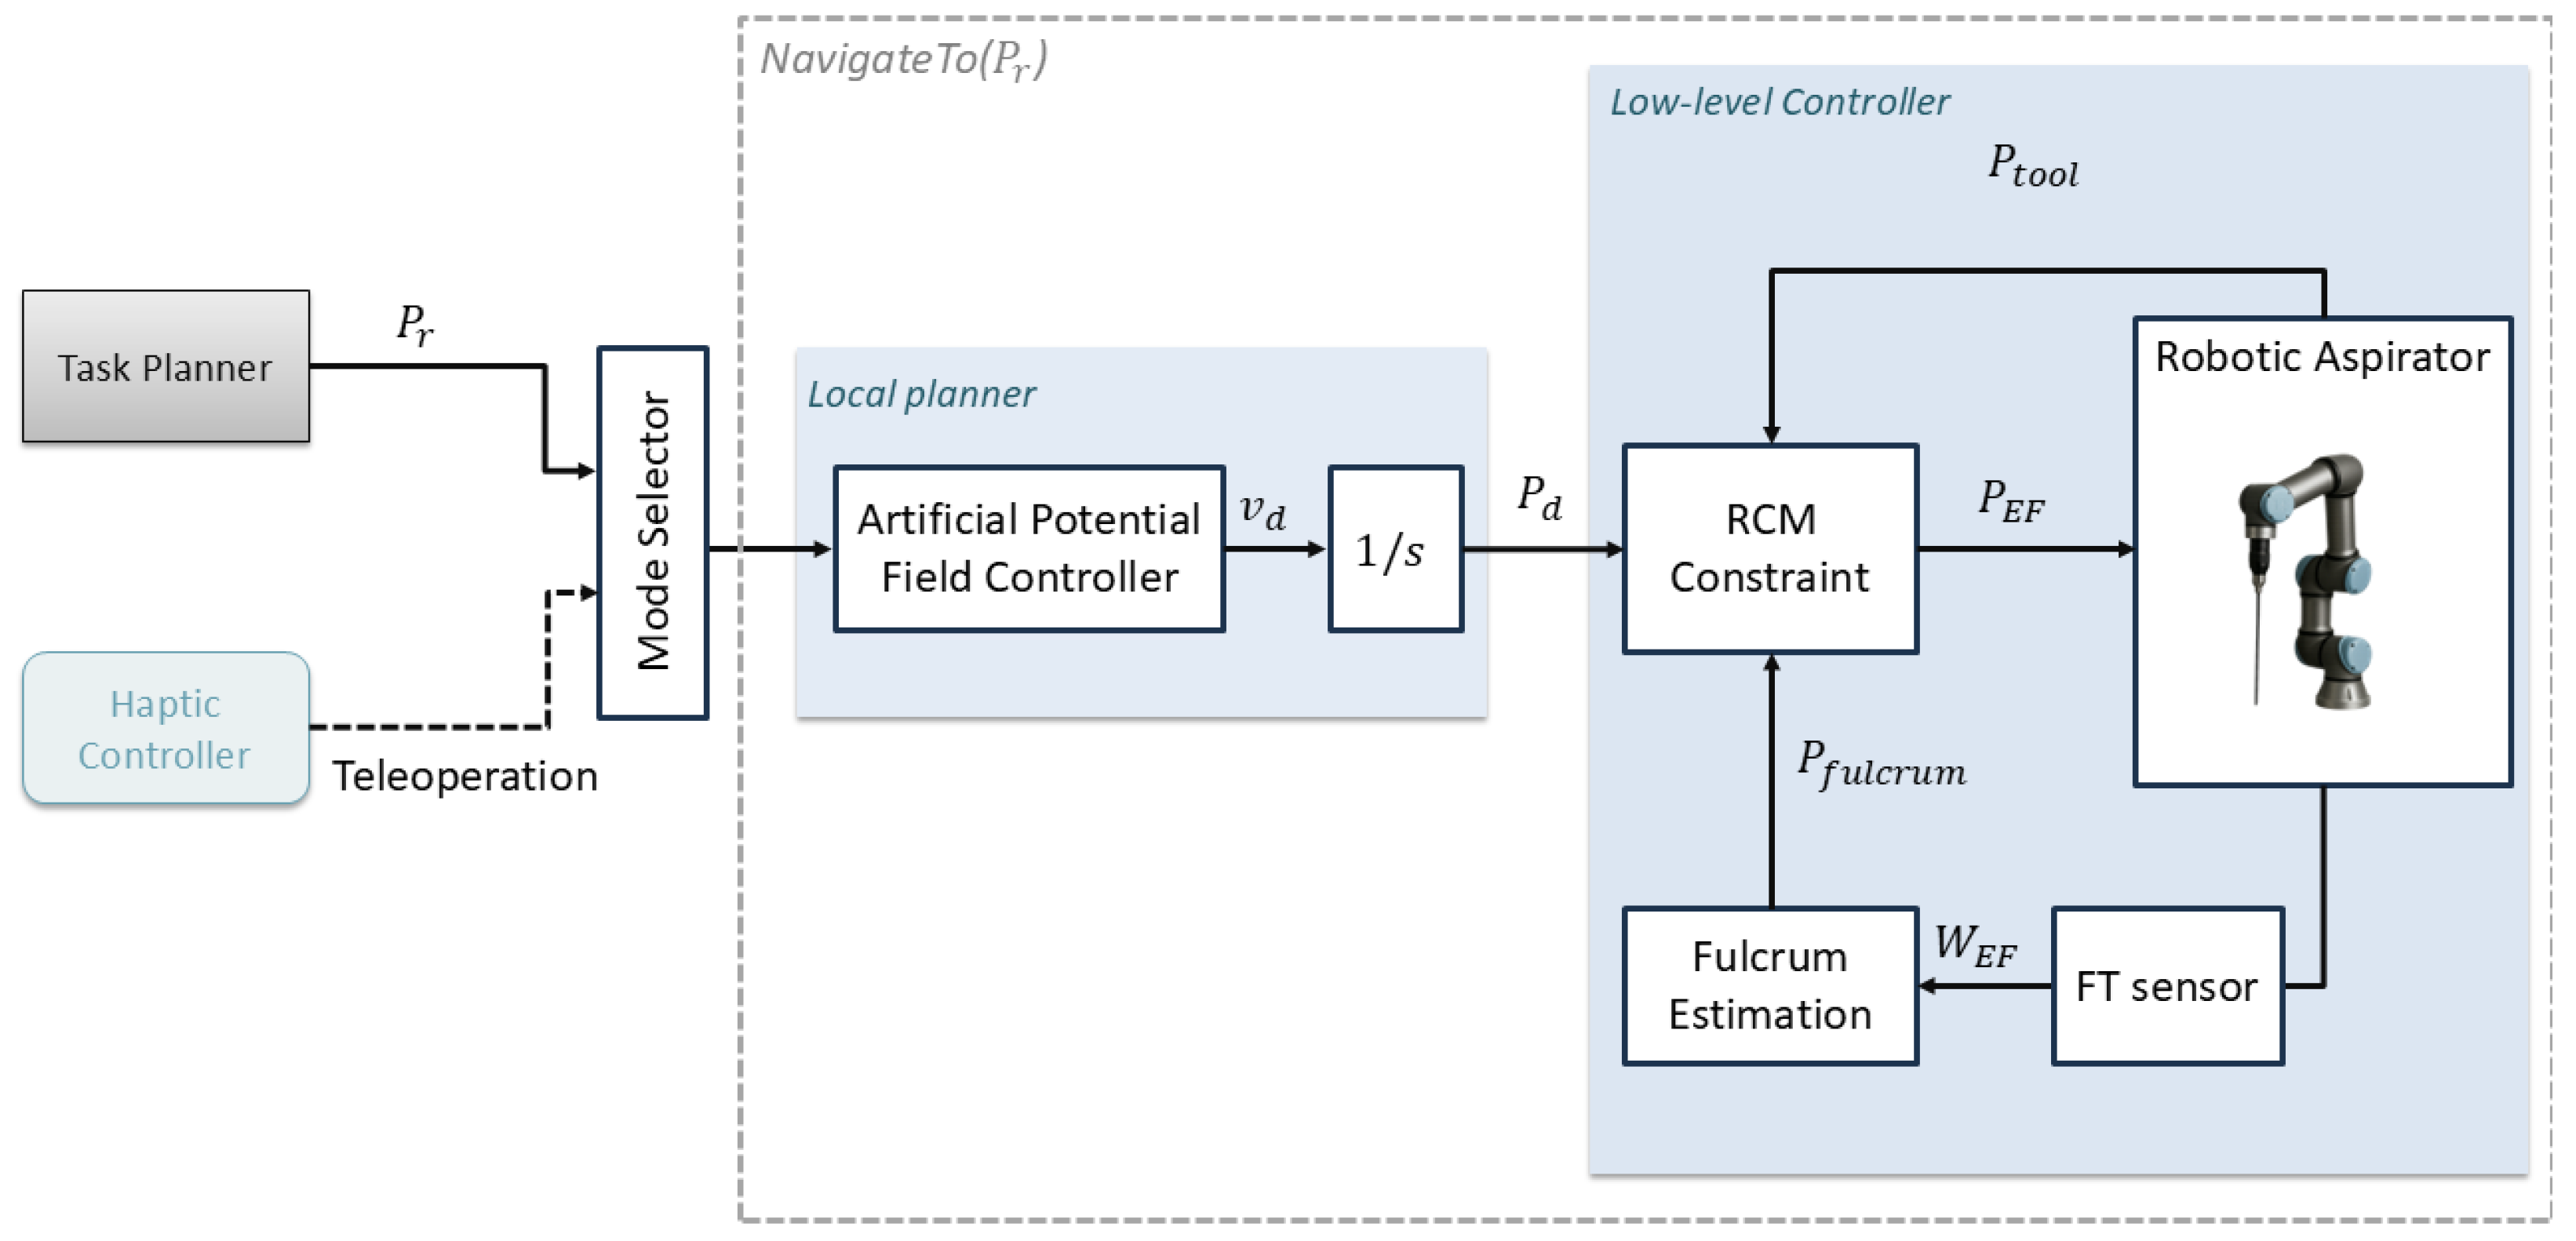
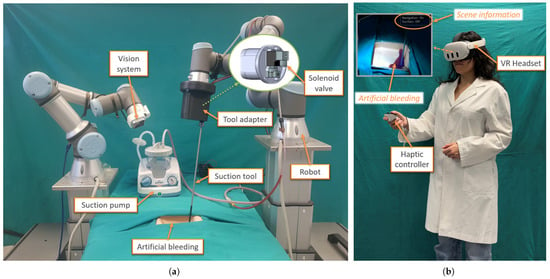
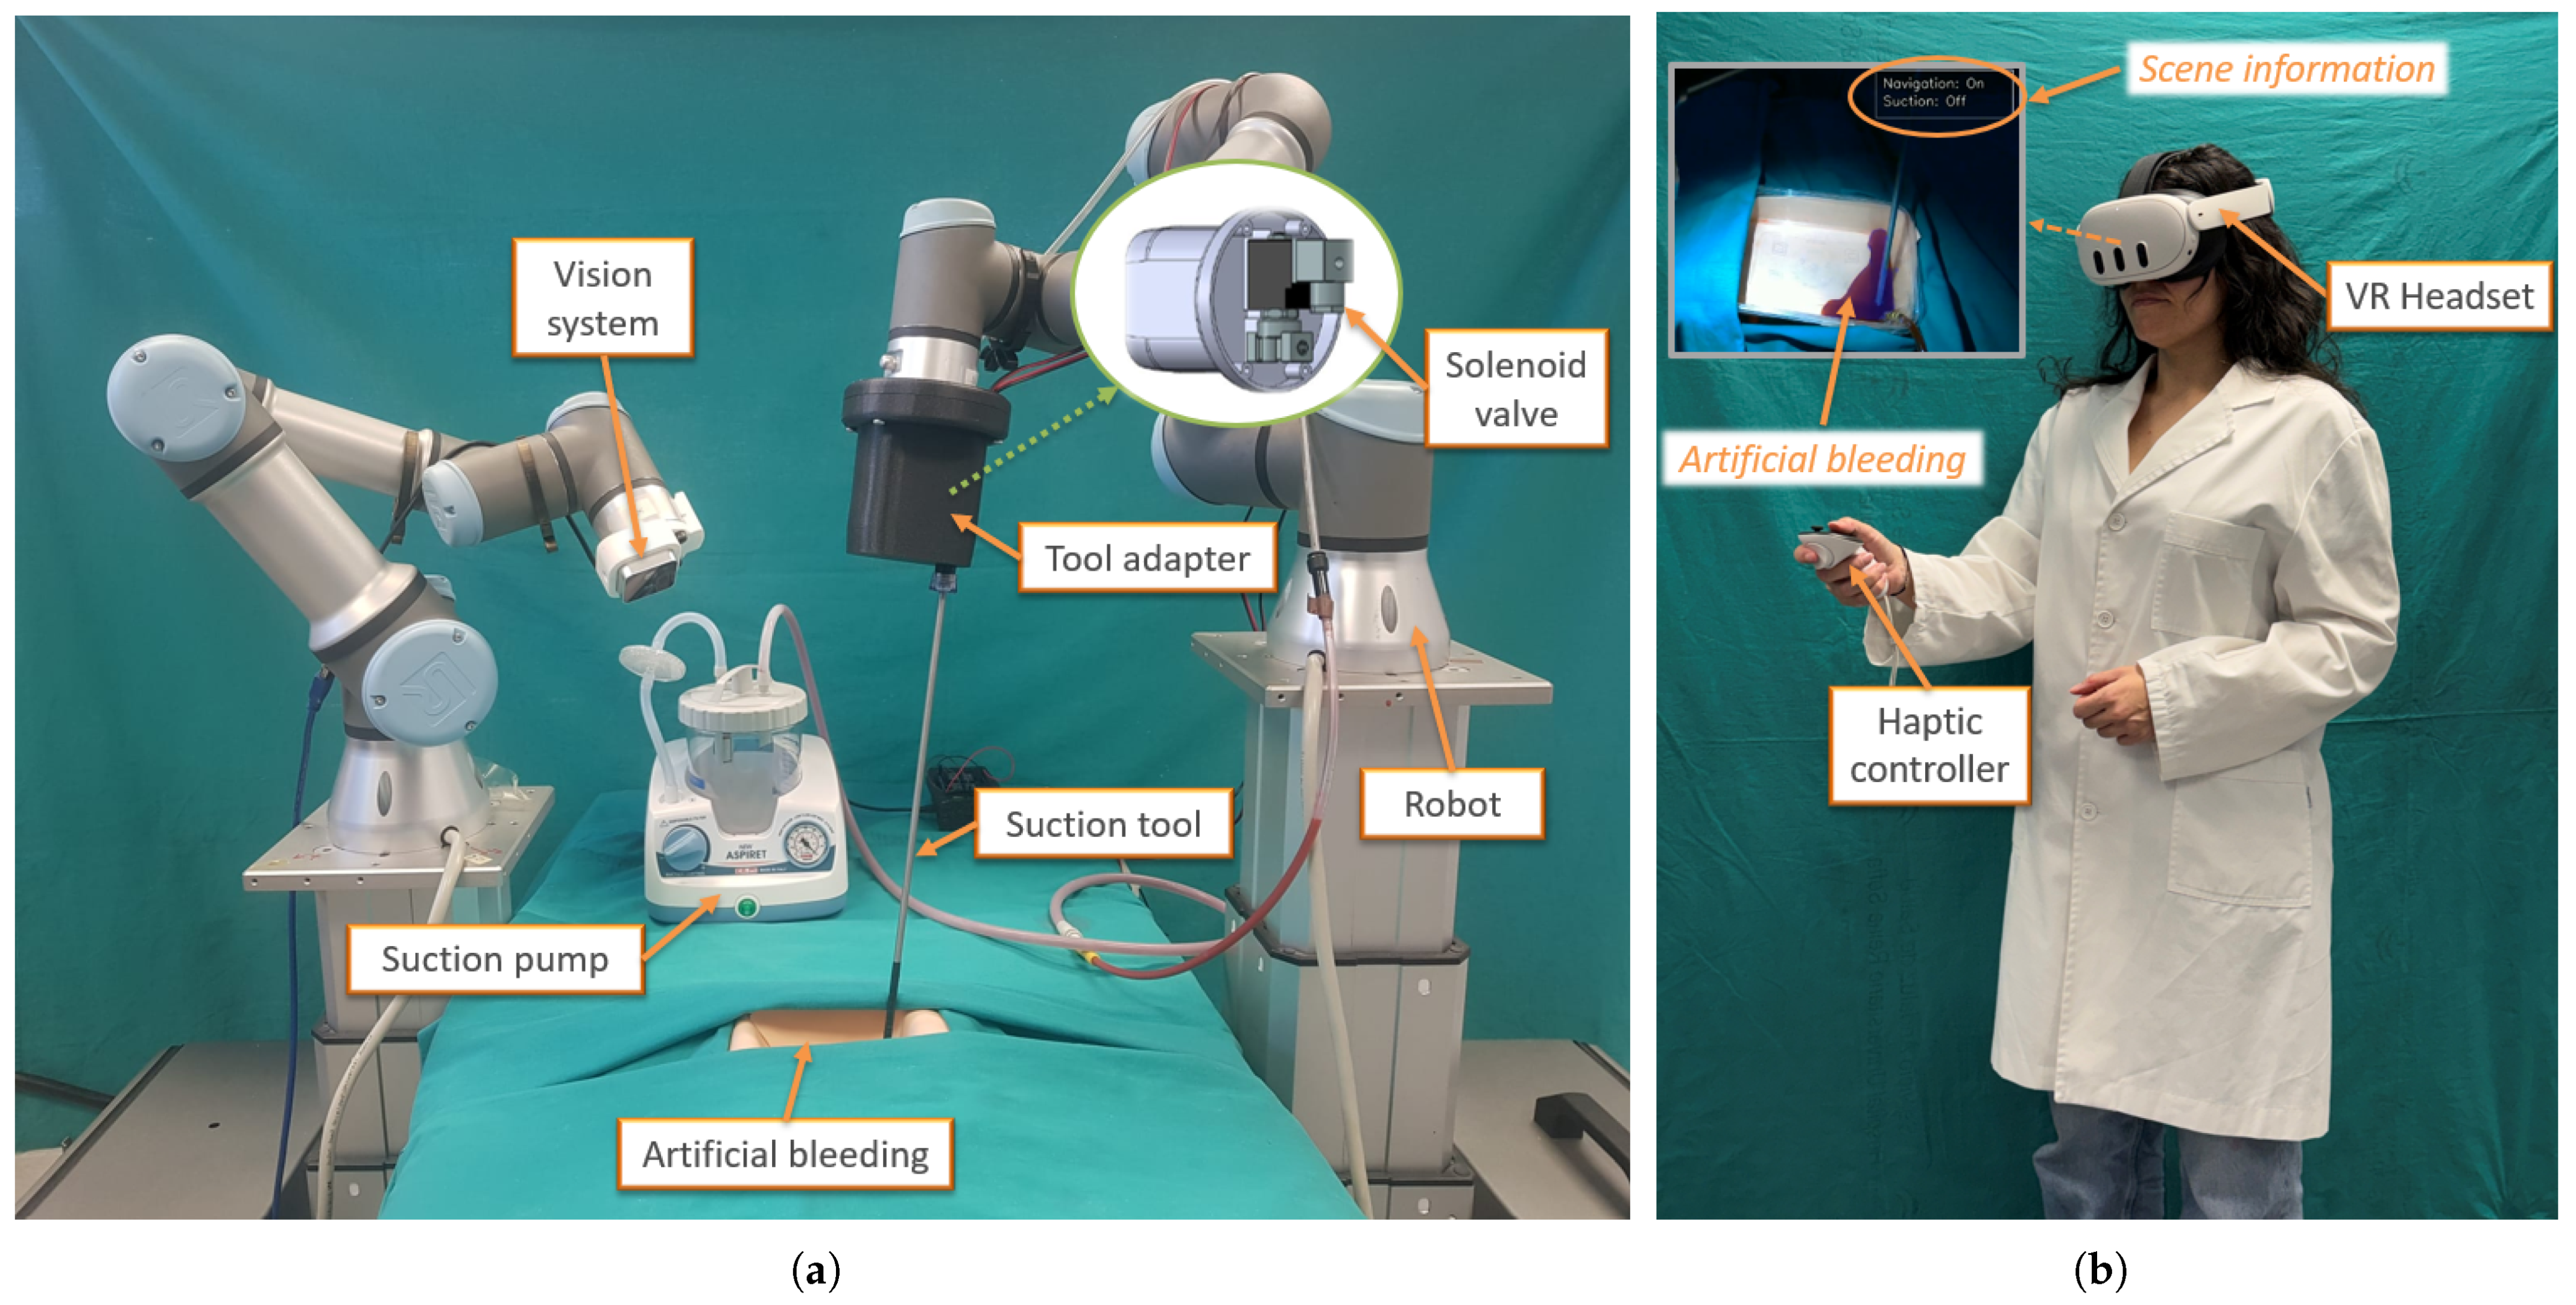
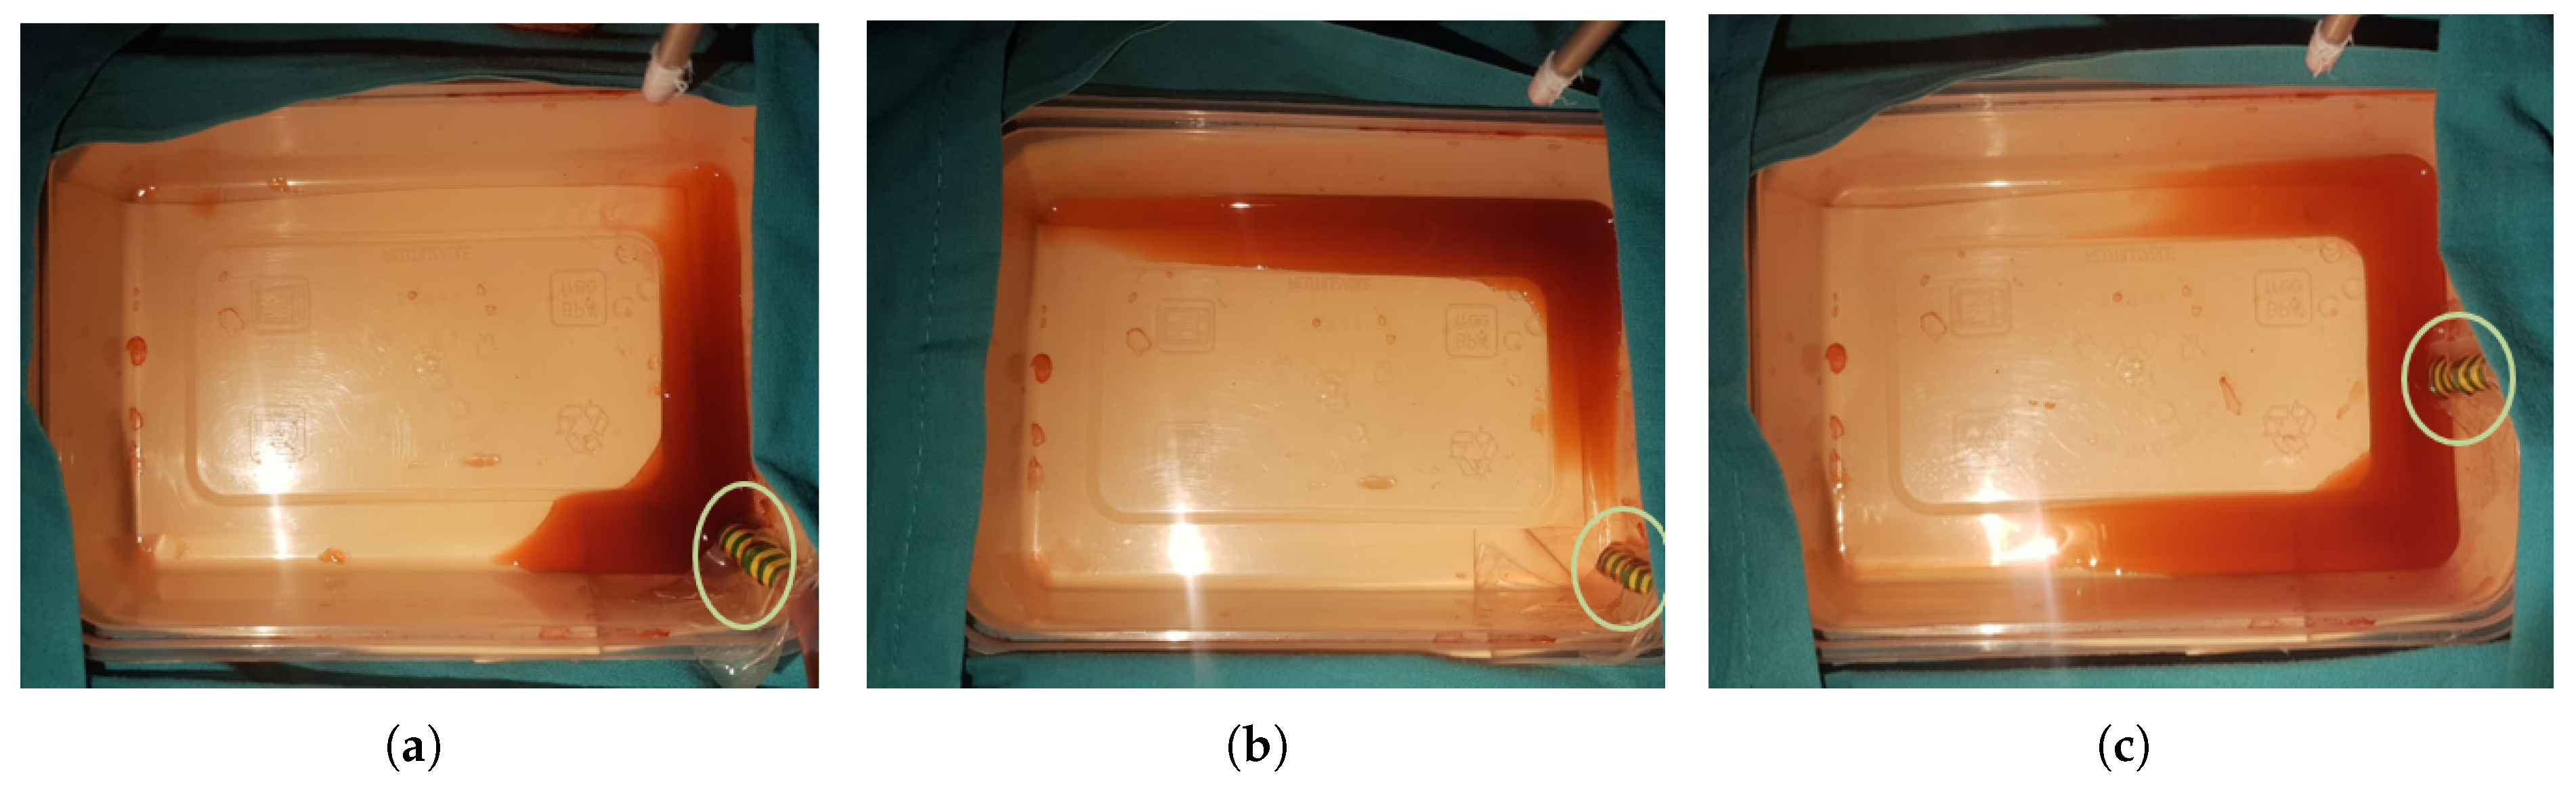
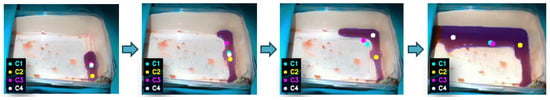
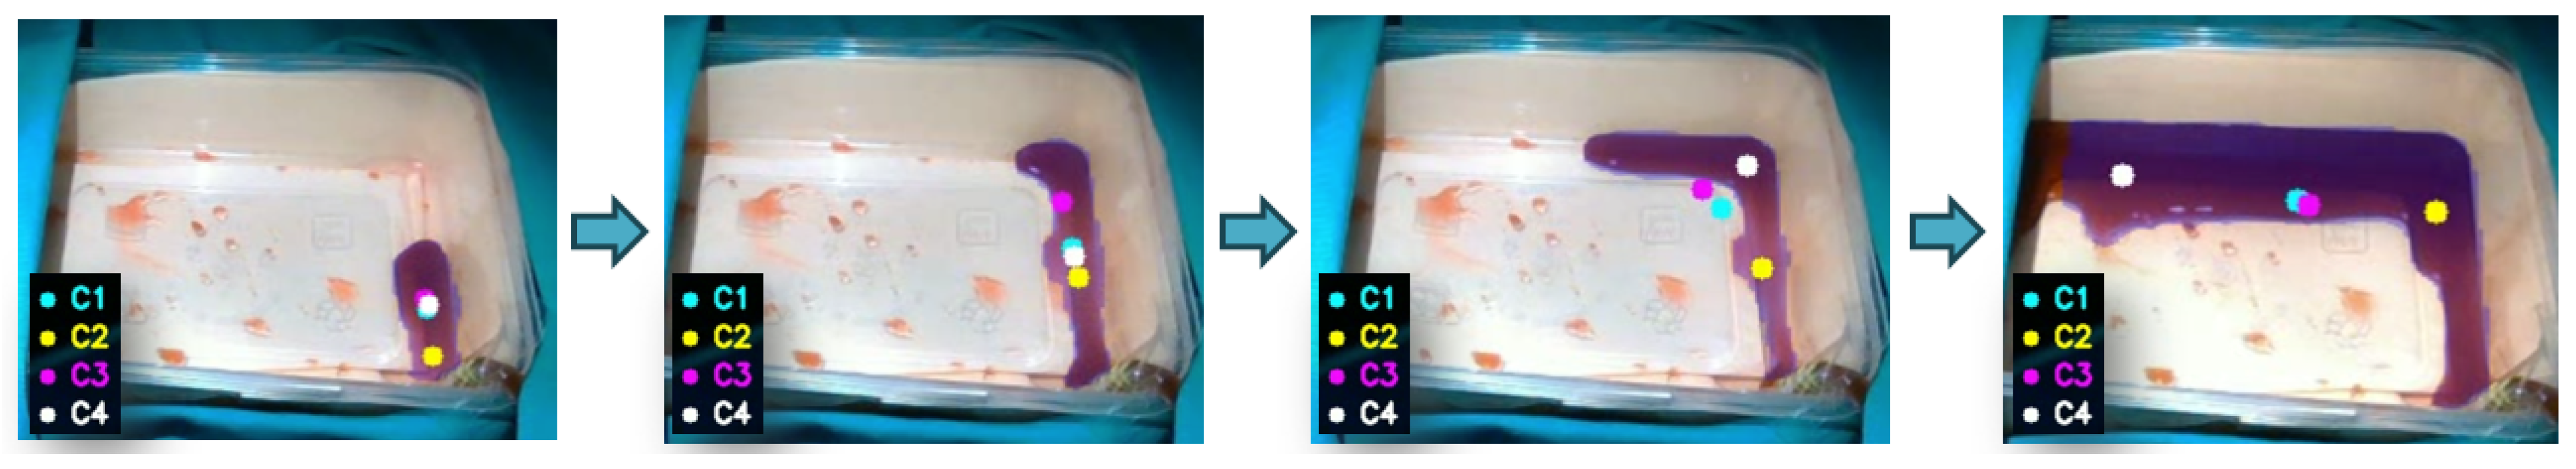
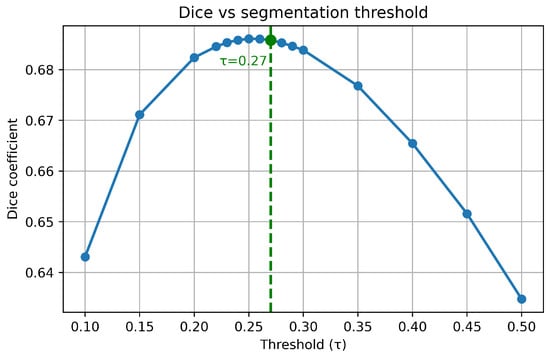
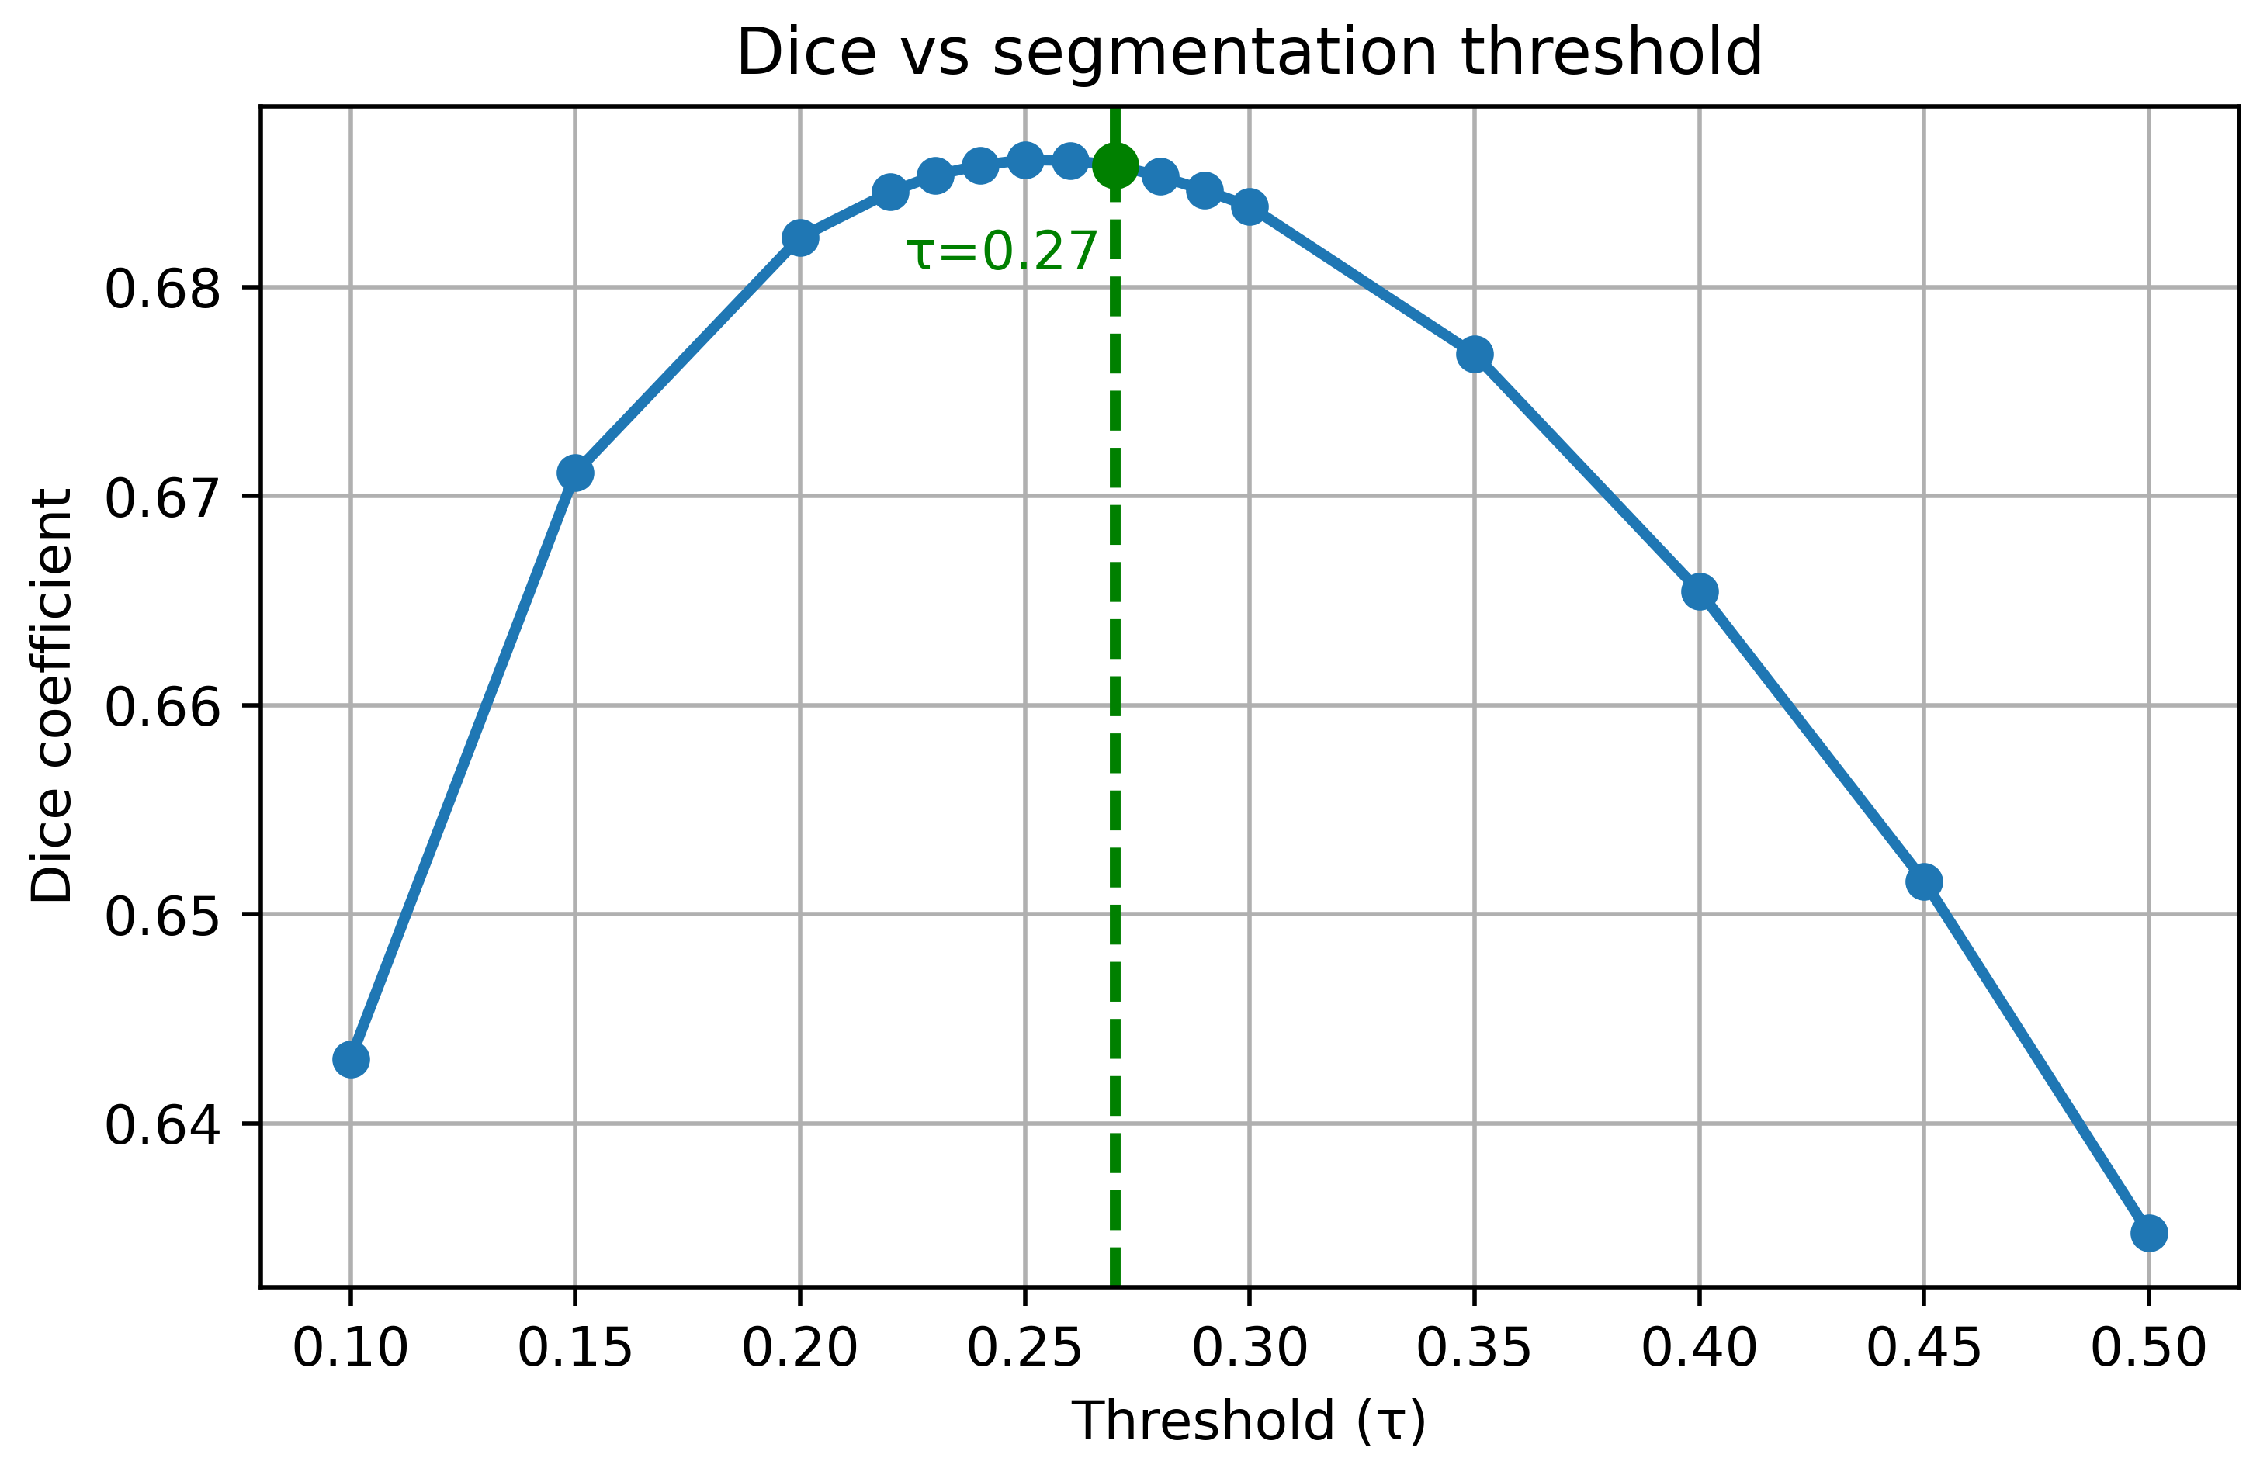
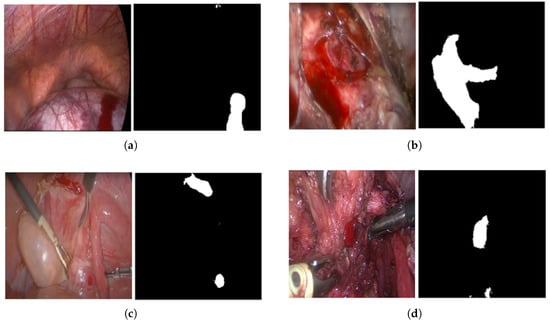
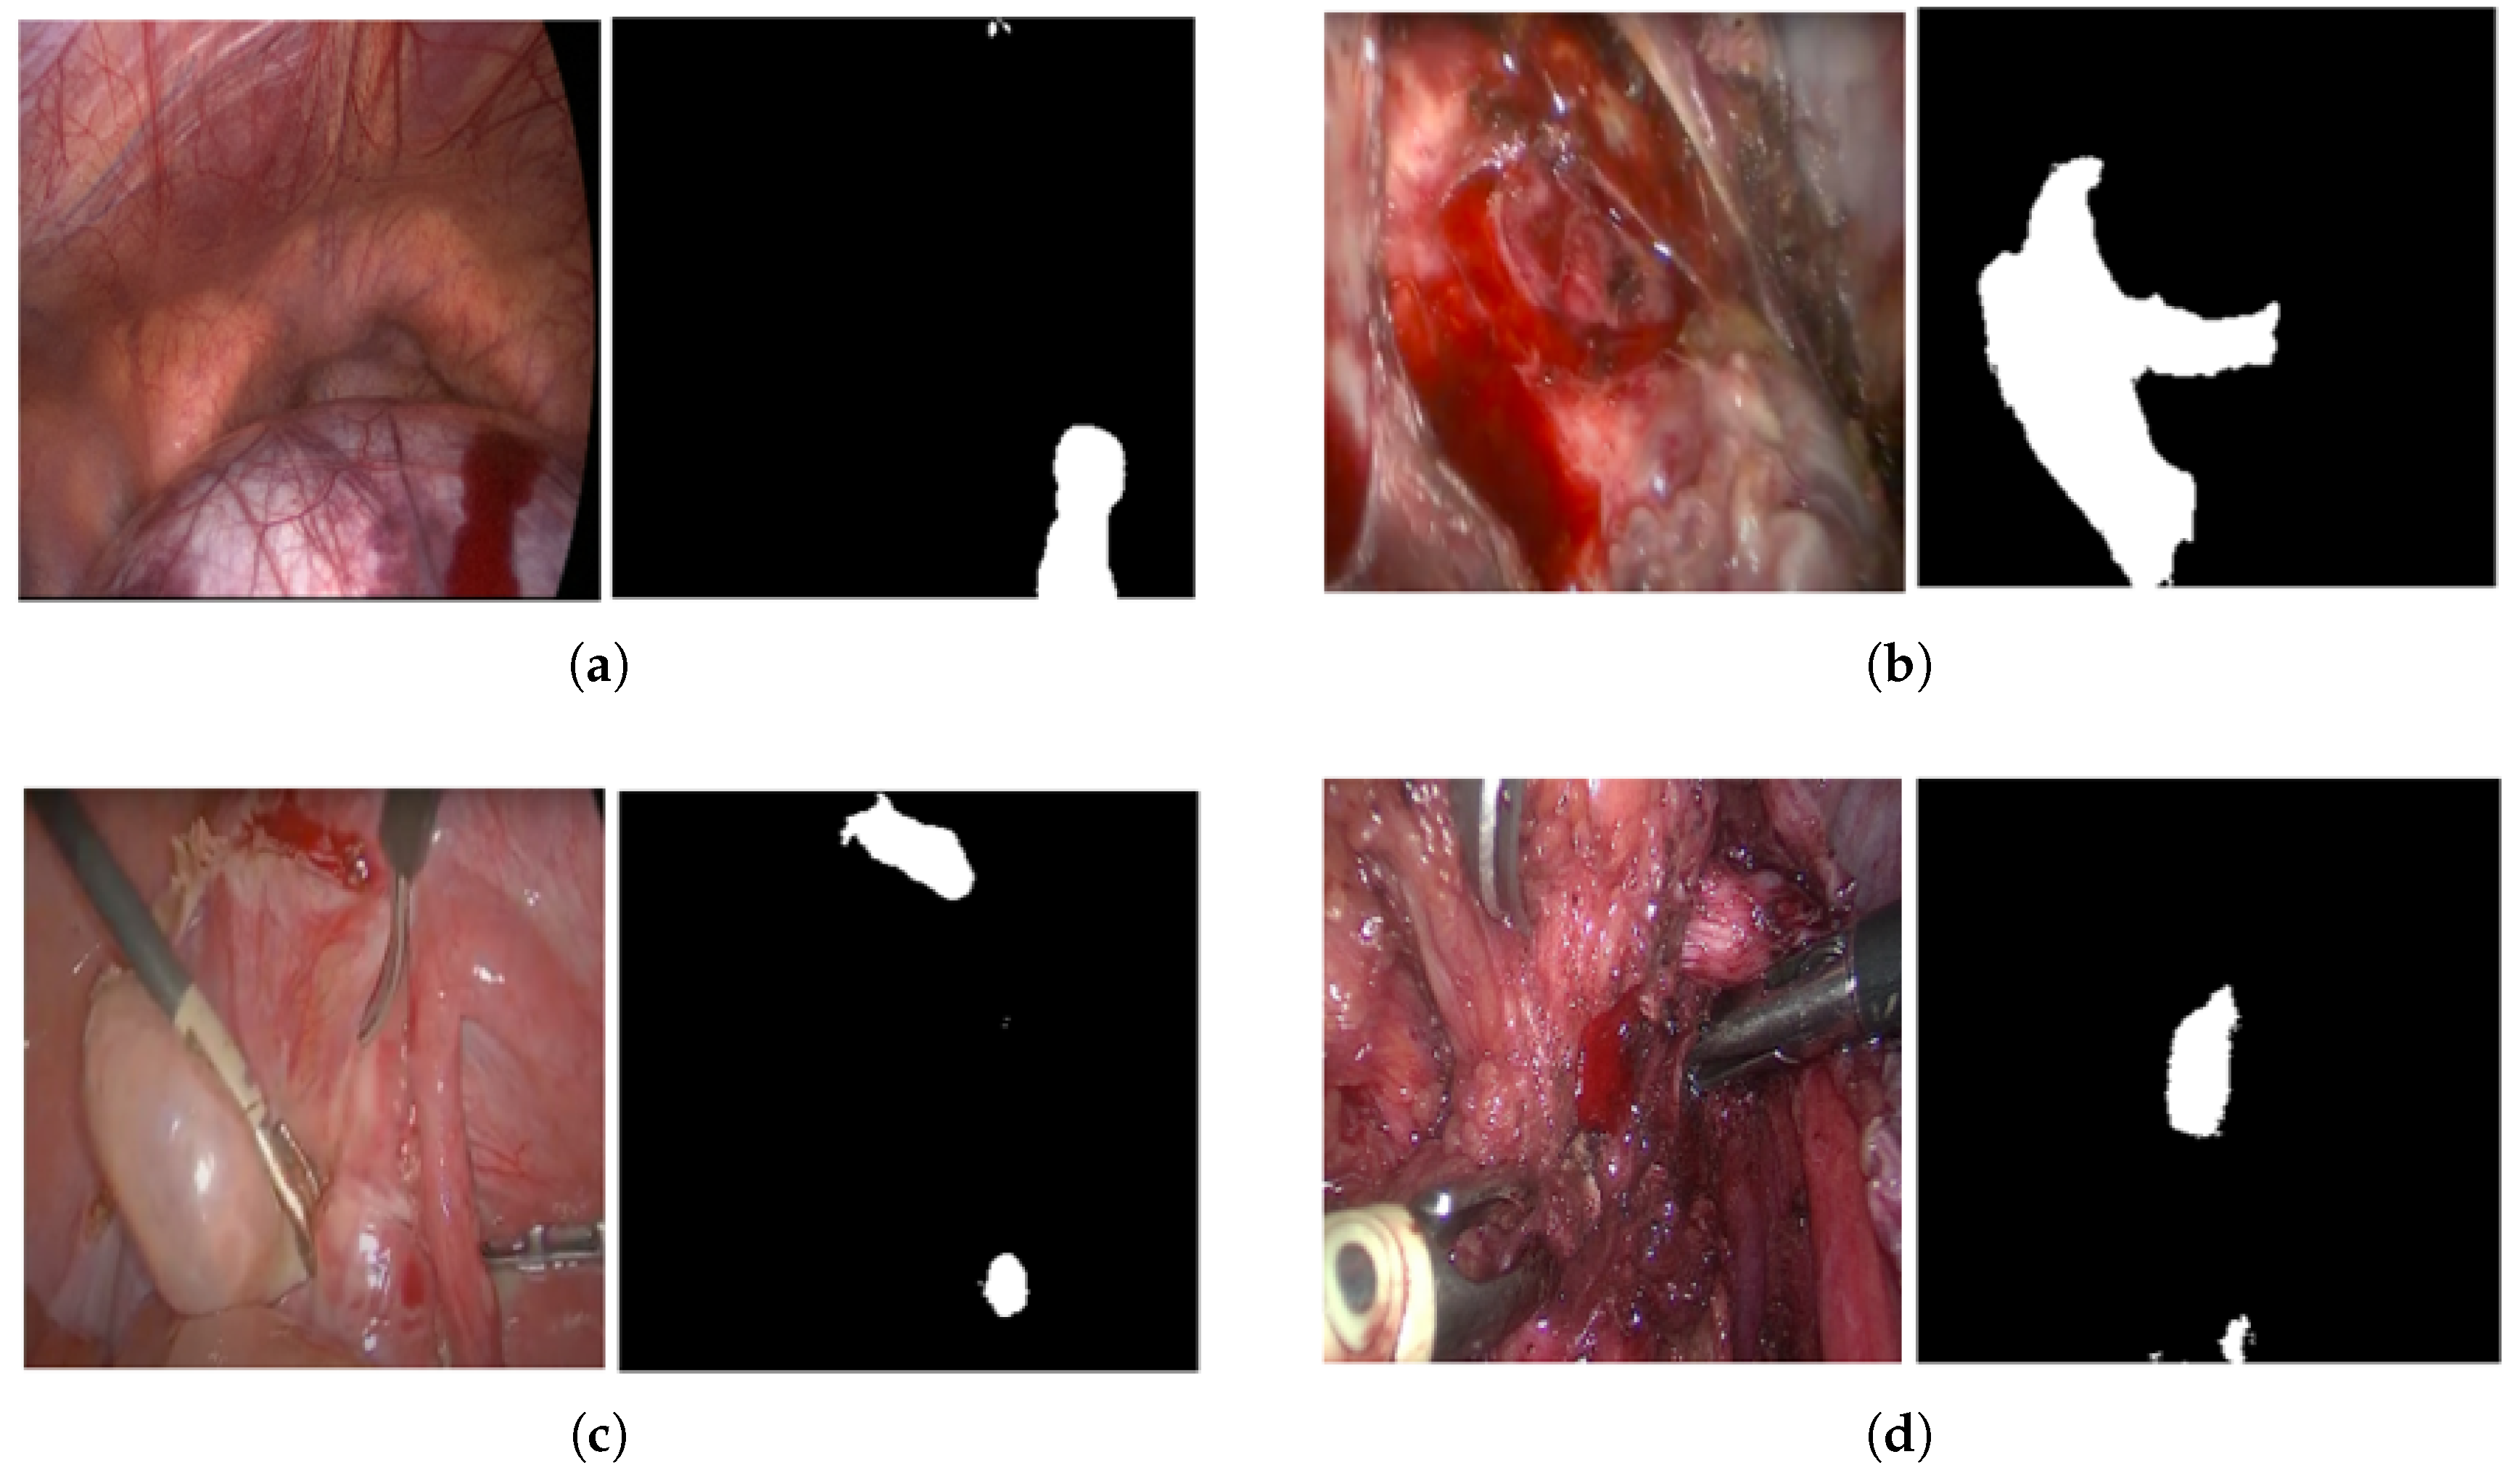
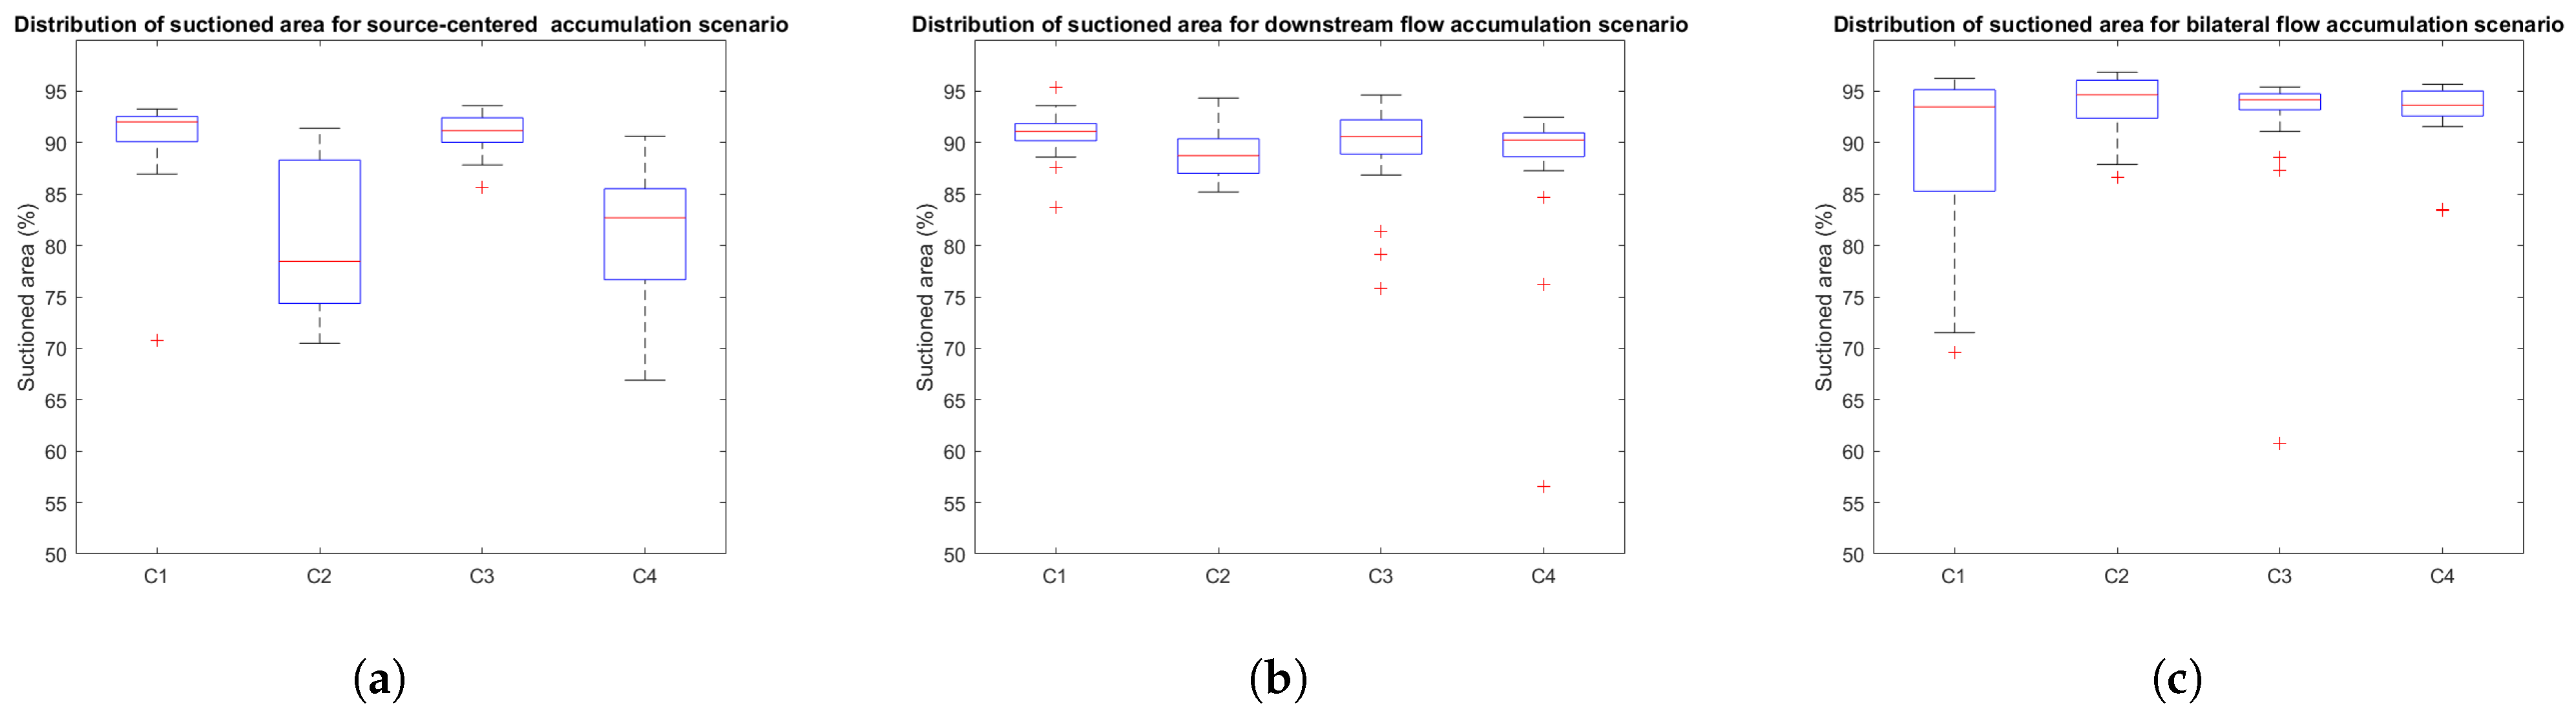

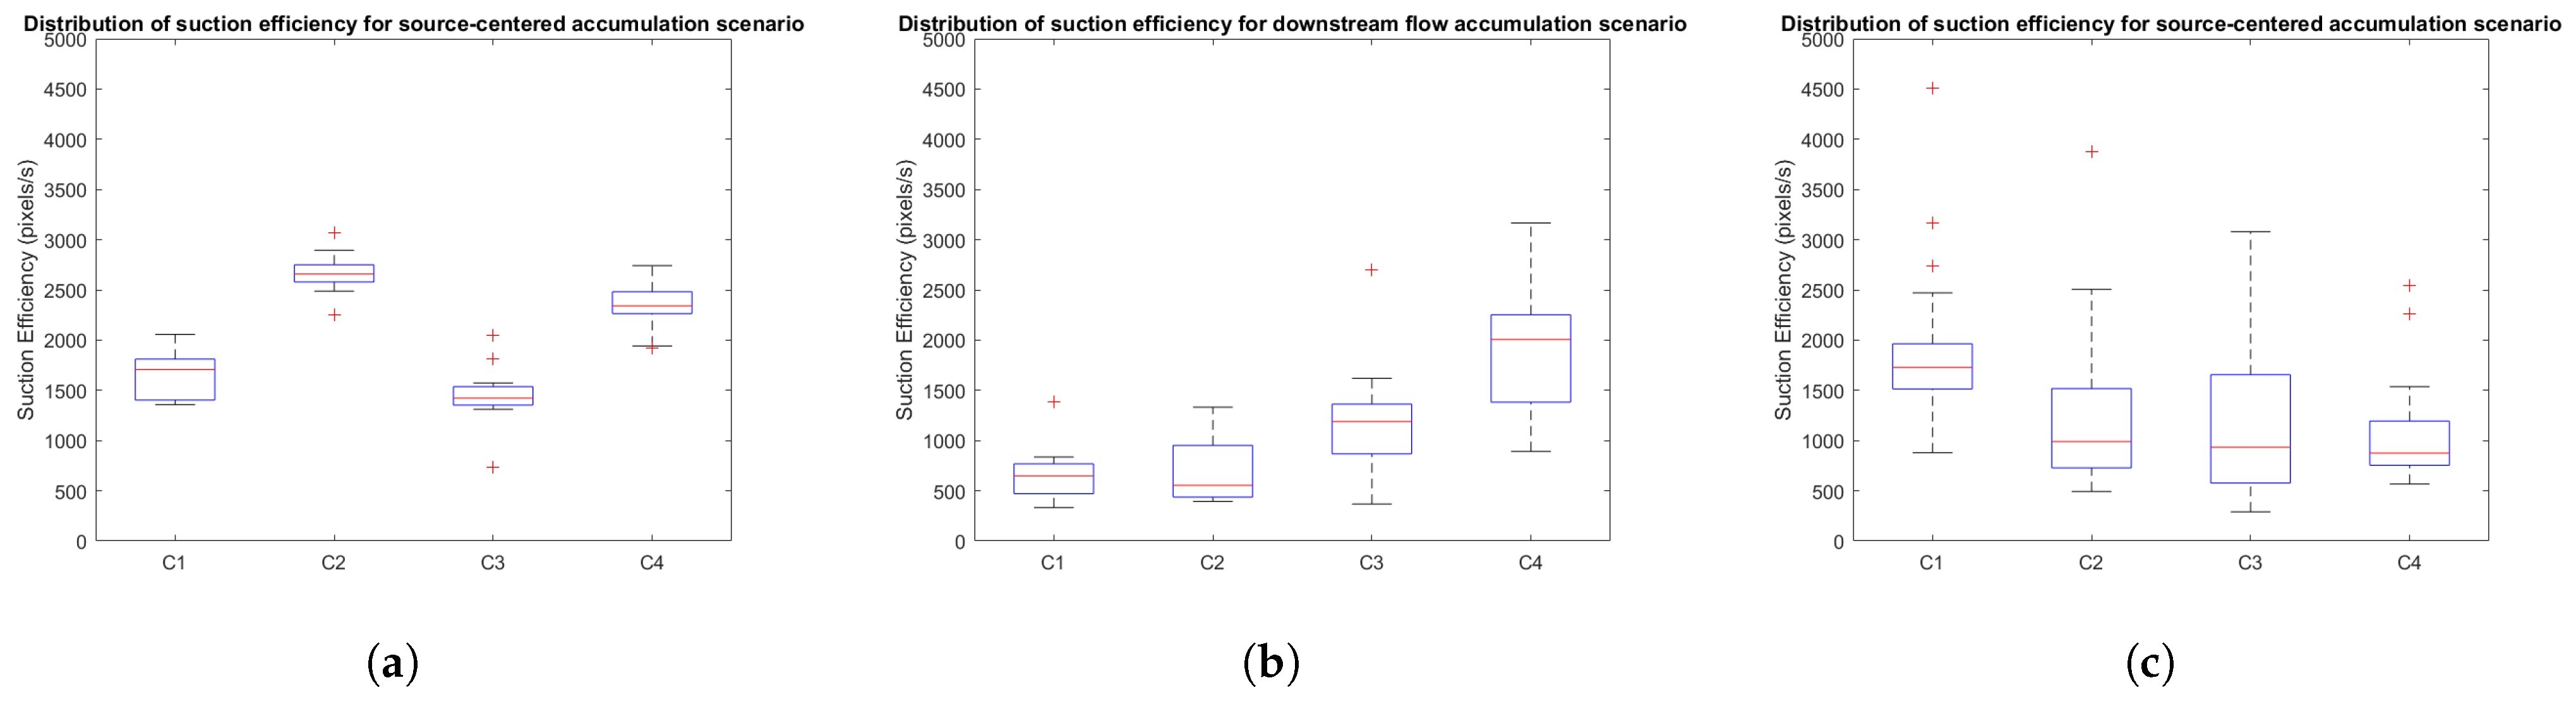
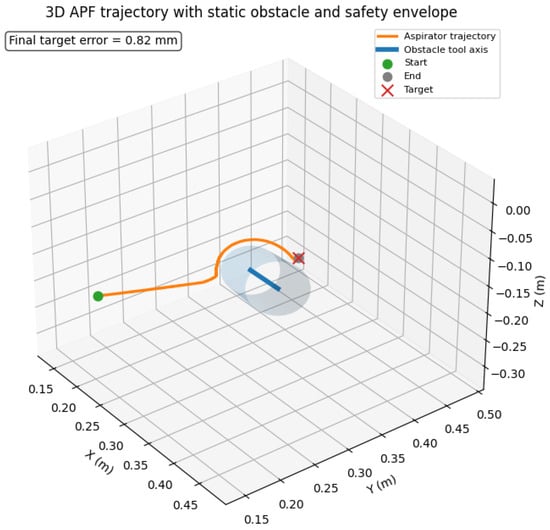
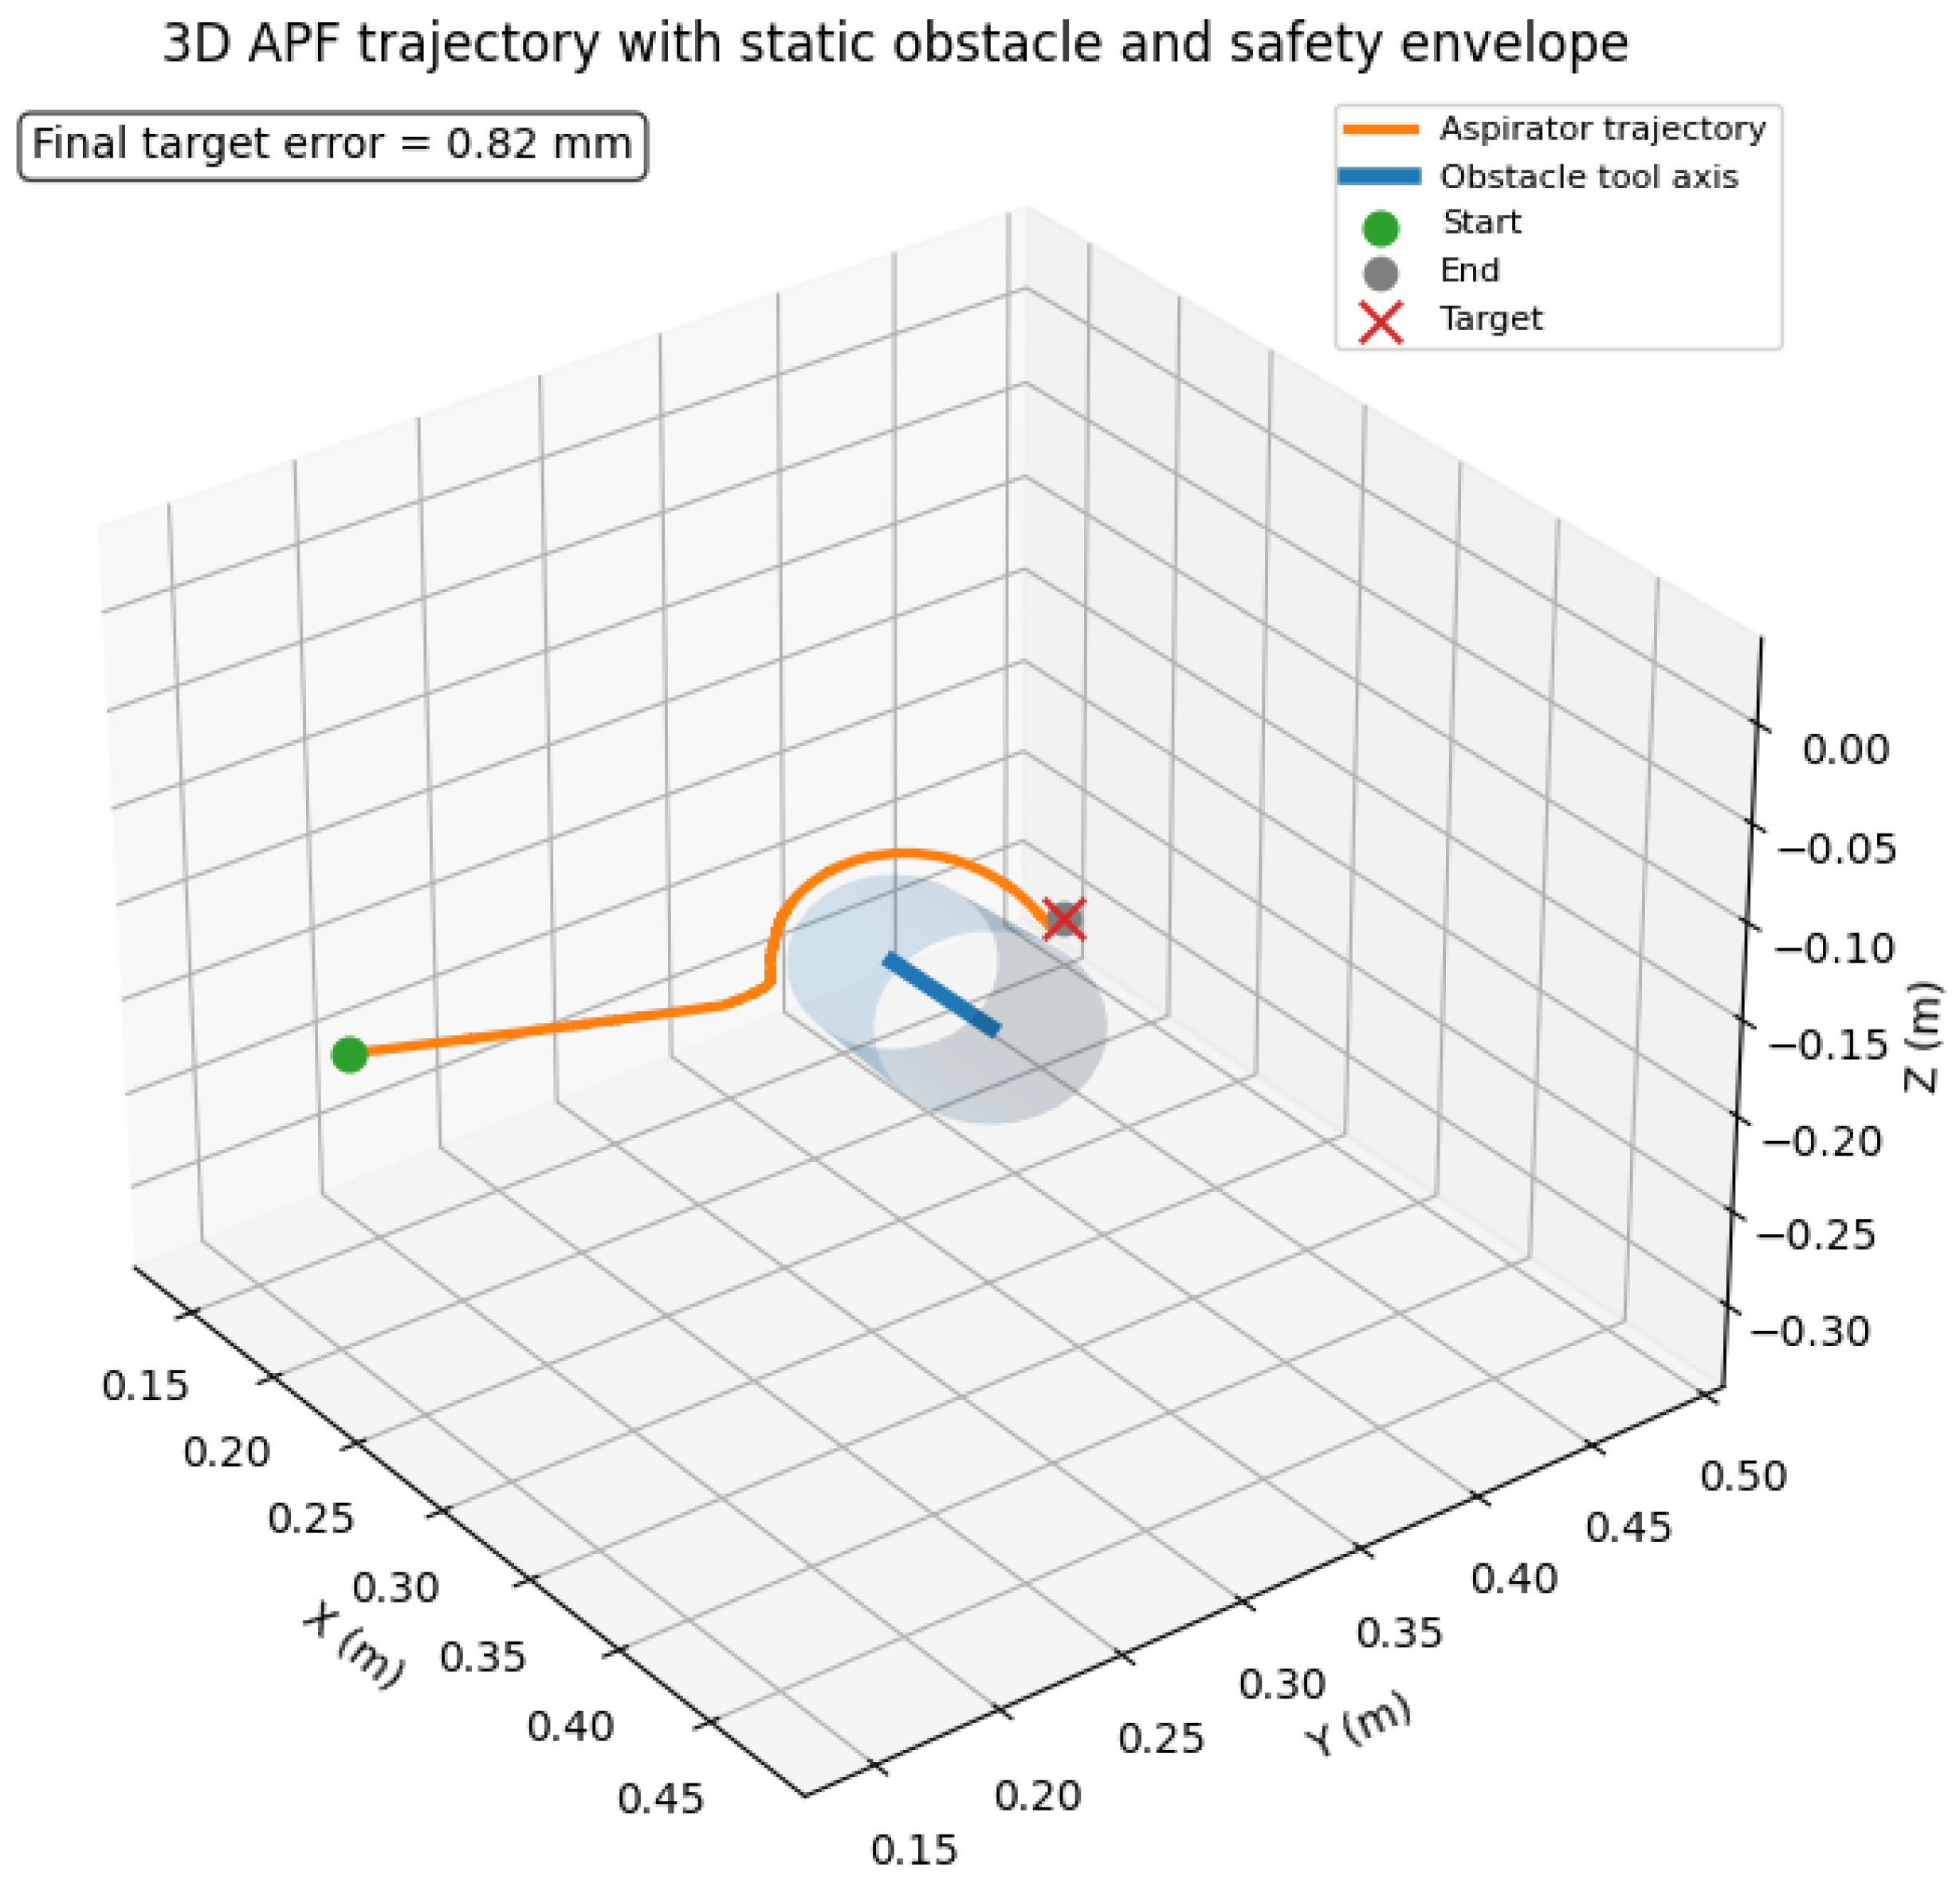
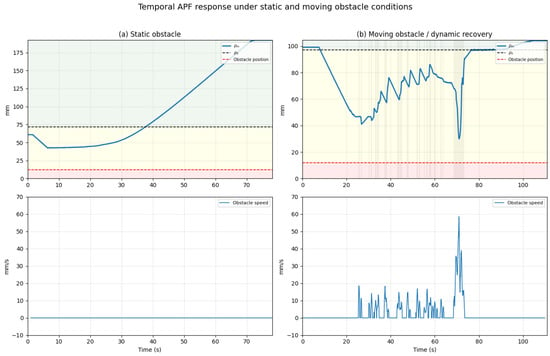
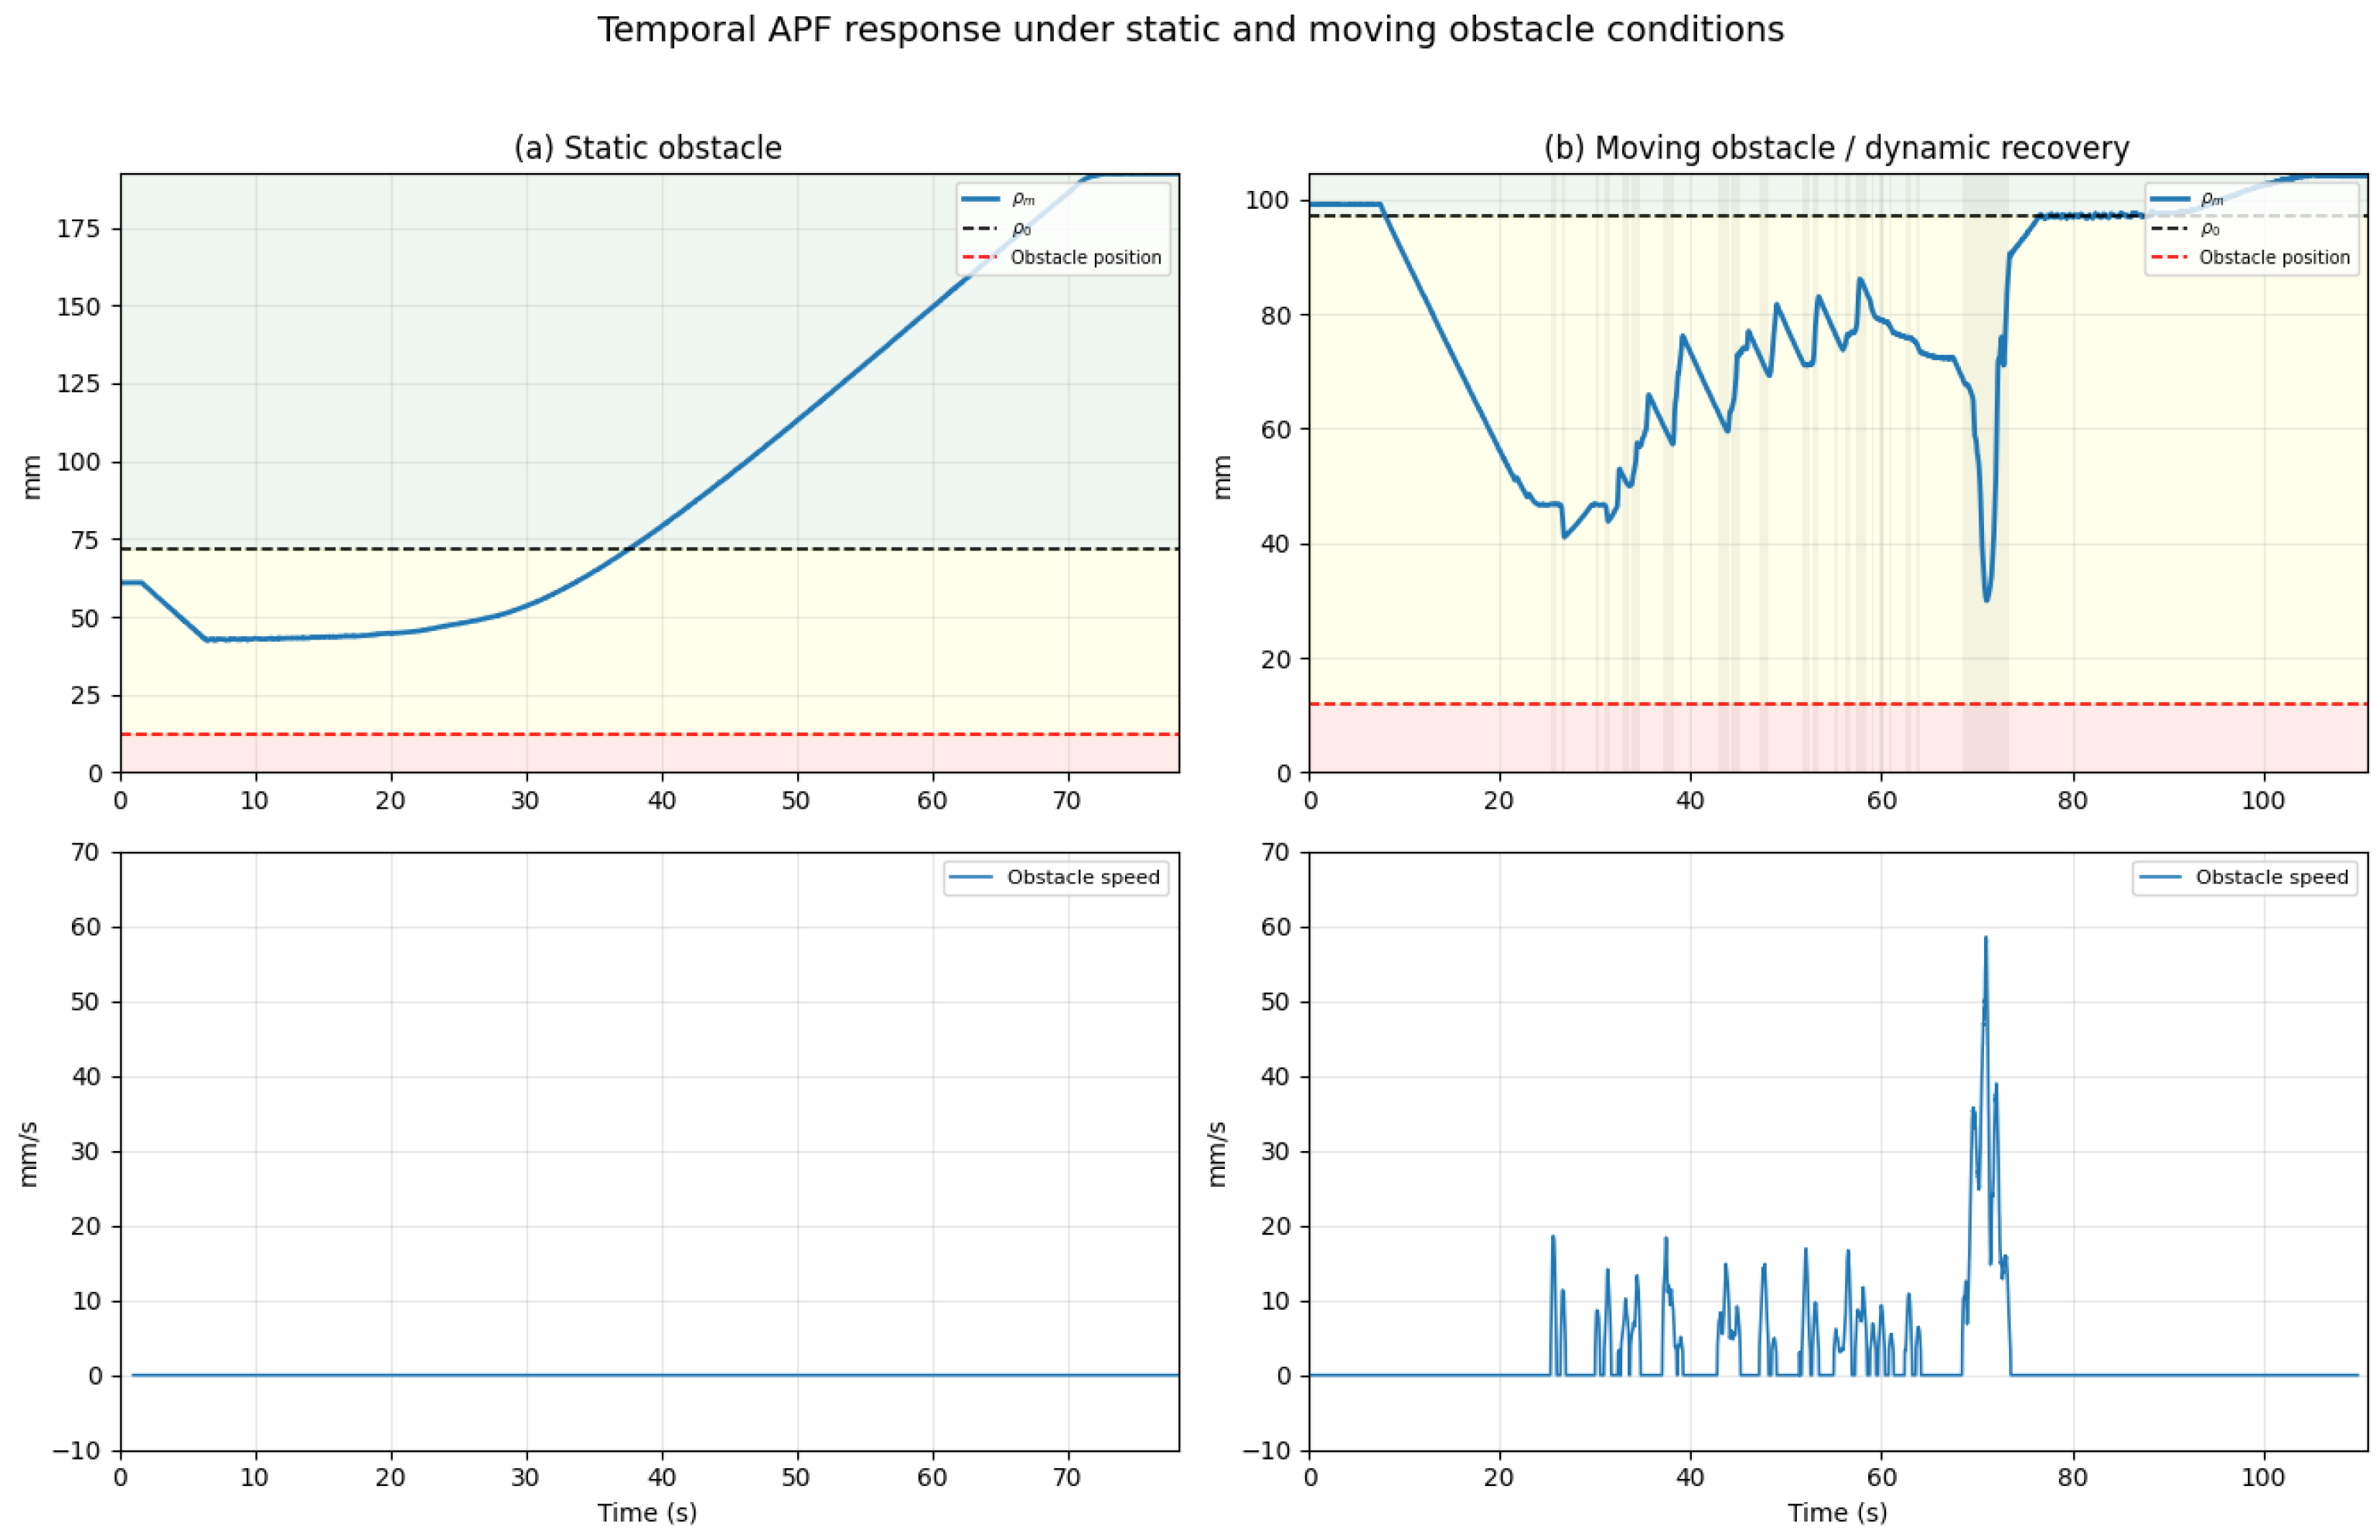

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.