


Preoperative Hyperlactatemia Predicts Mortality in Acute Stanford Type A Dissection: A 16-Year-Period, Single-Center, Retrospective Study
 , , ,
 and
Abstract
1. Introduction
2. Methods
3. Statistical Analysis
4. Results
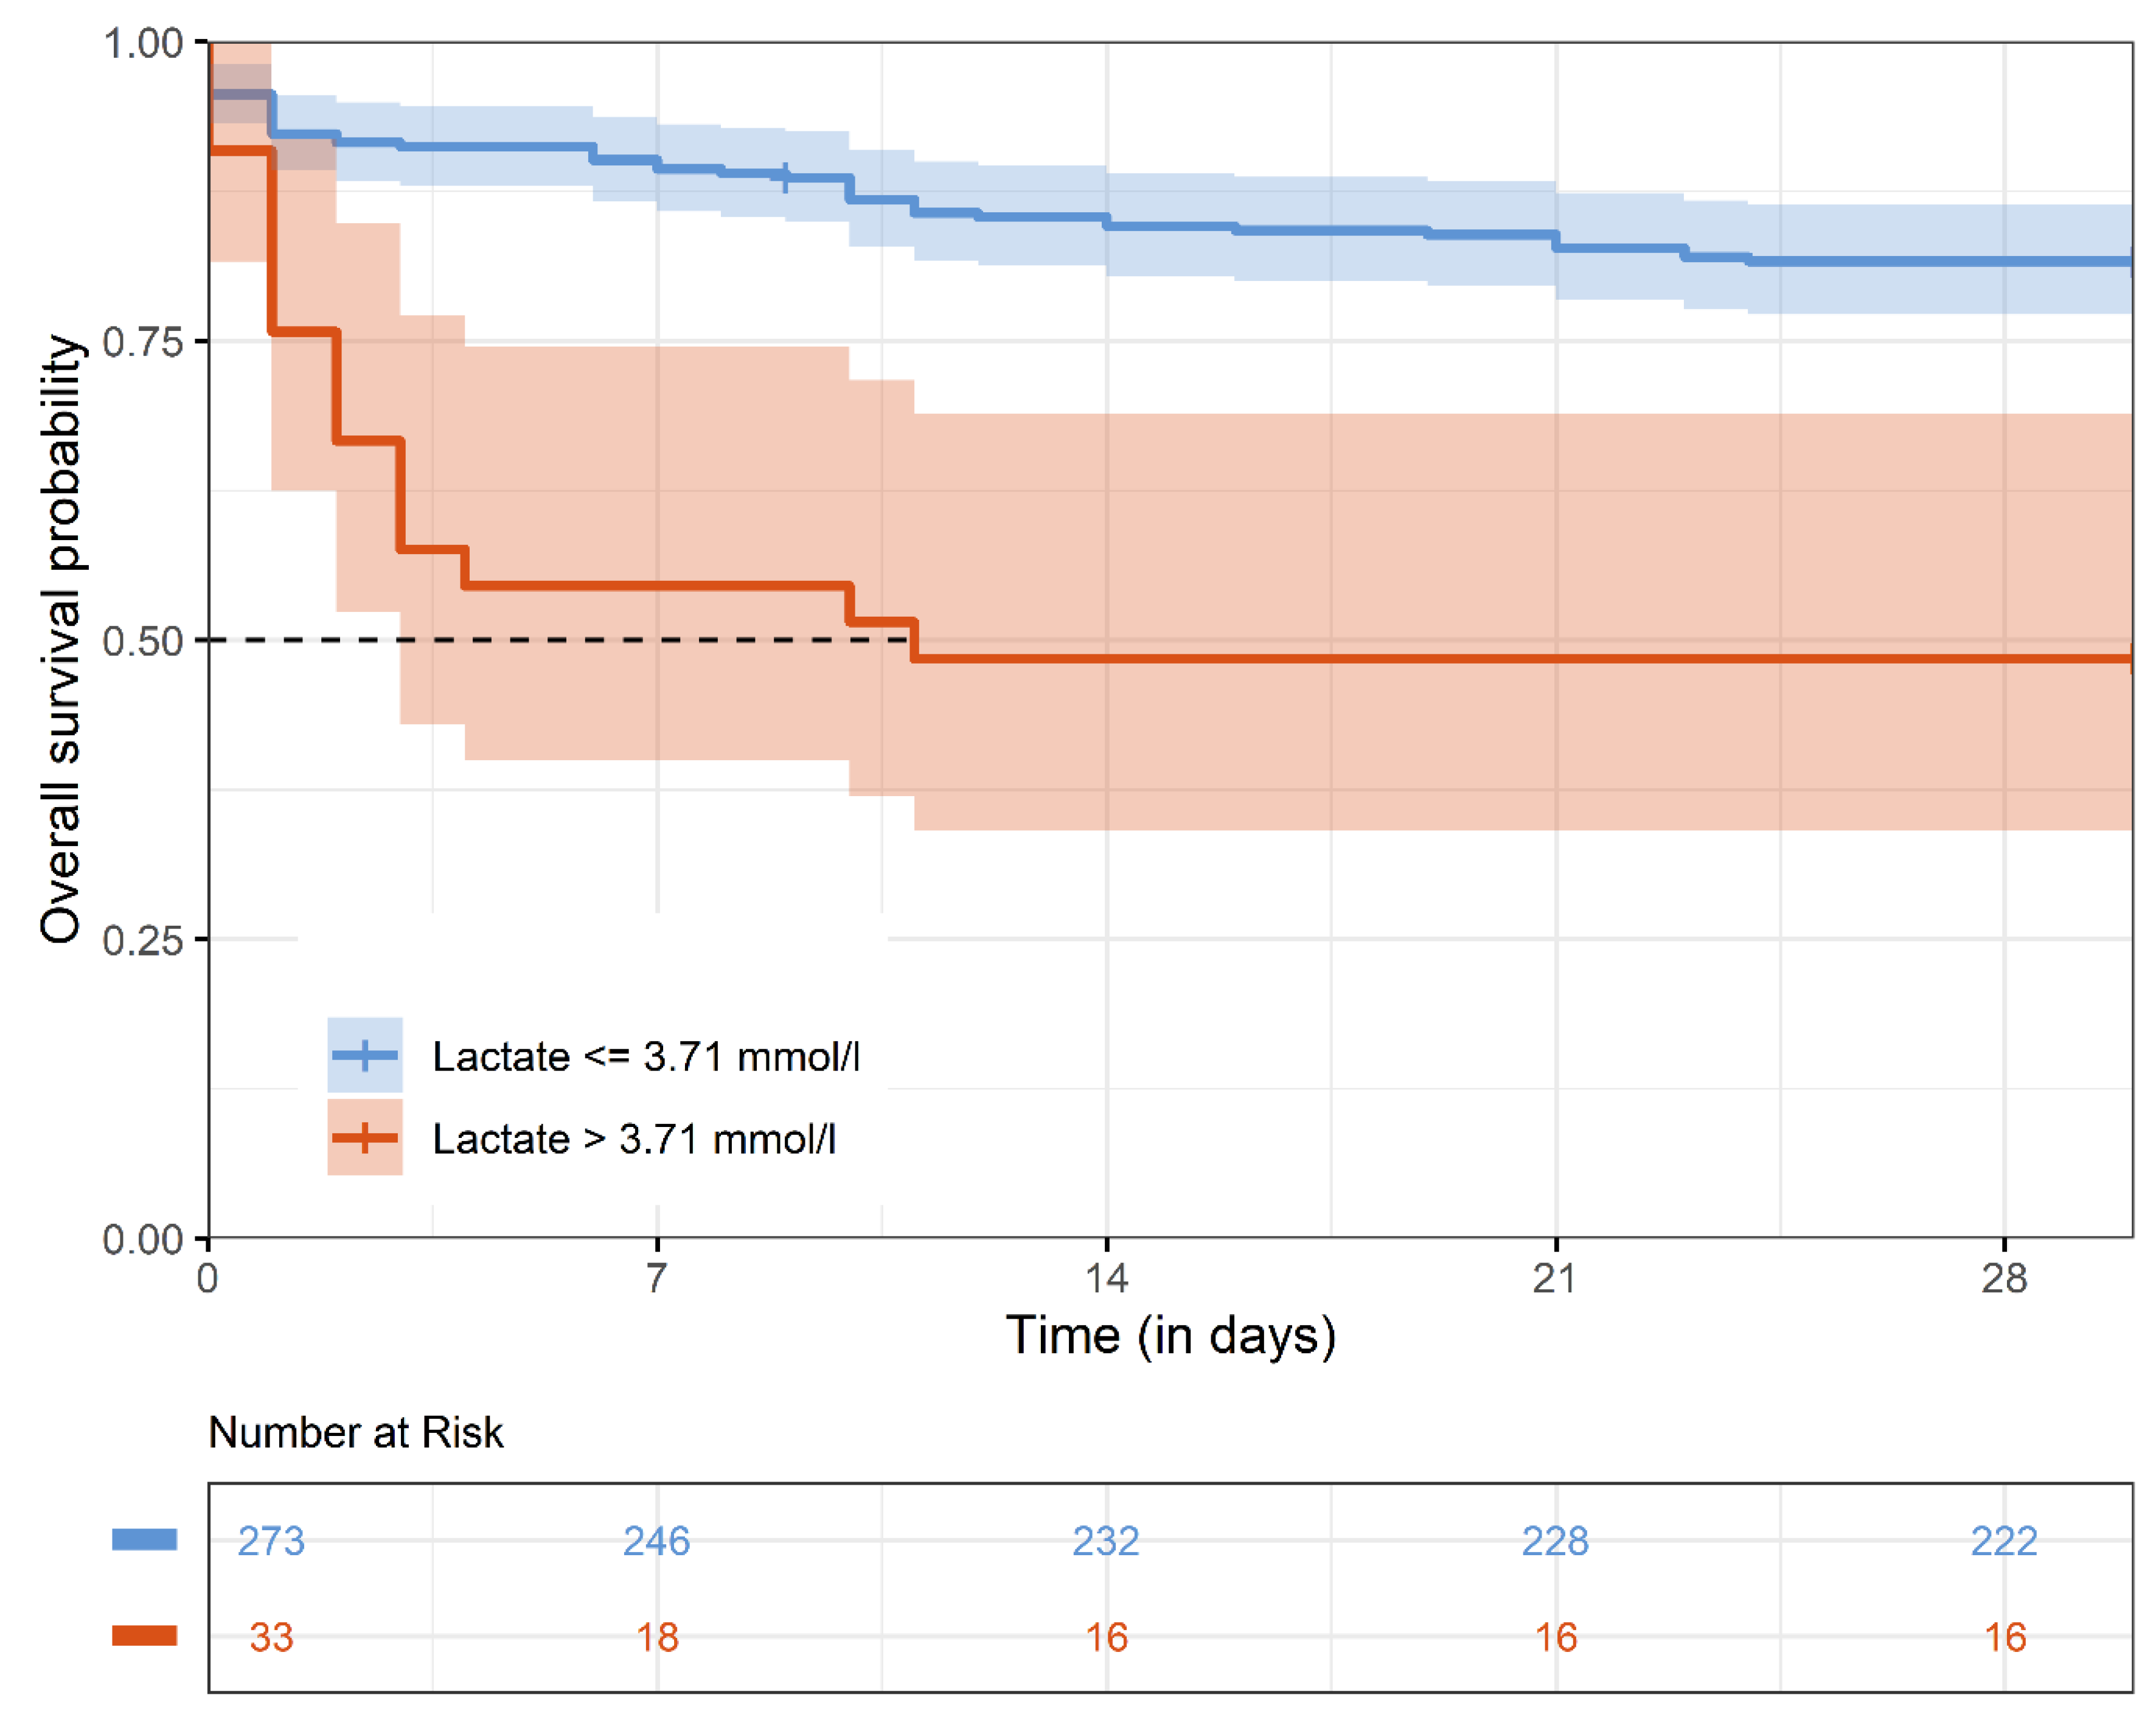
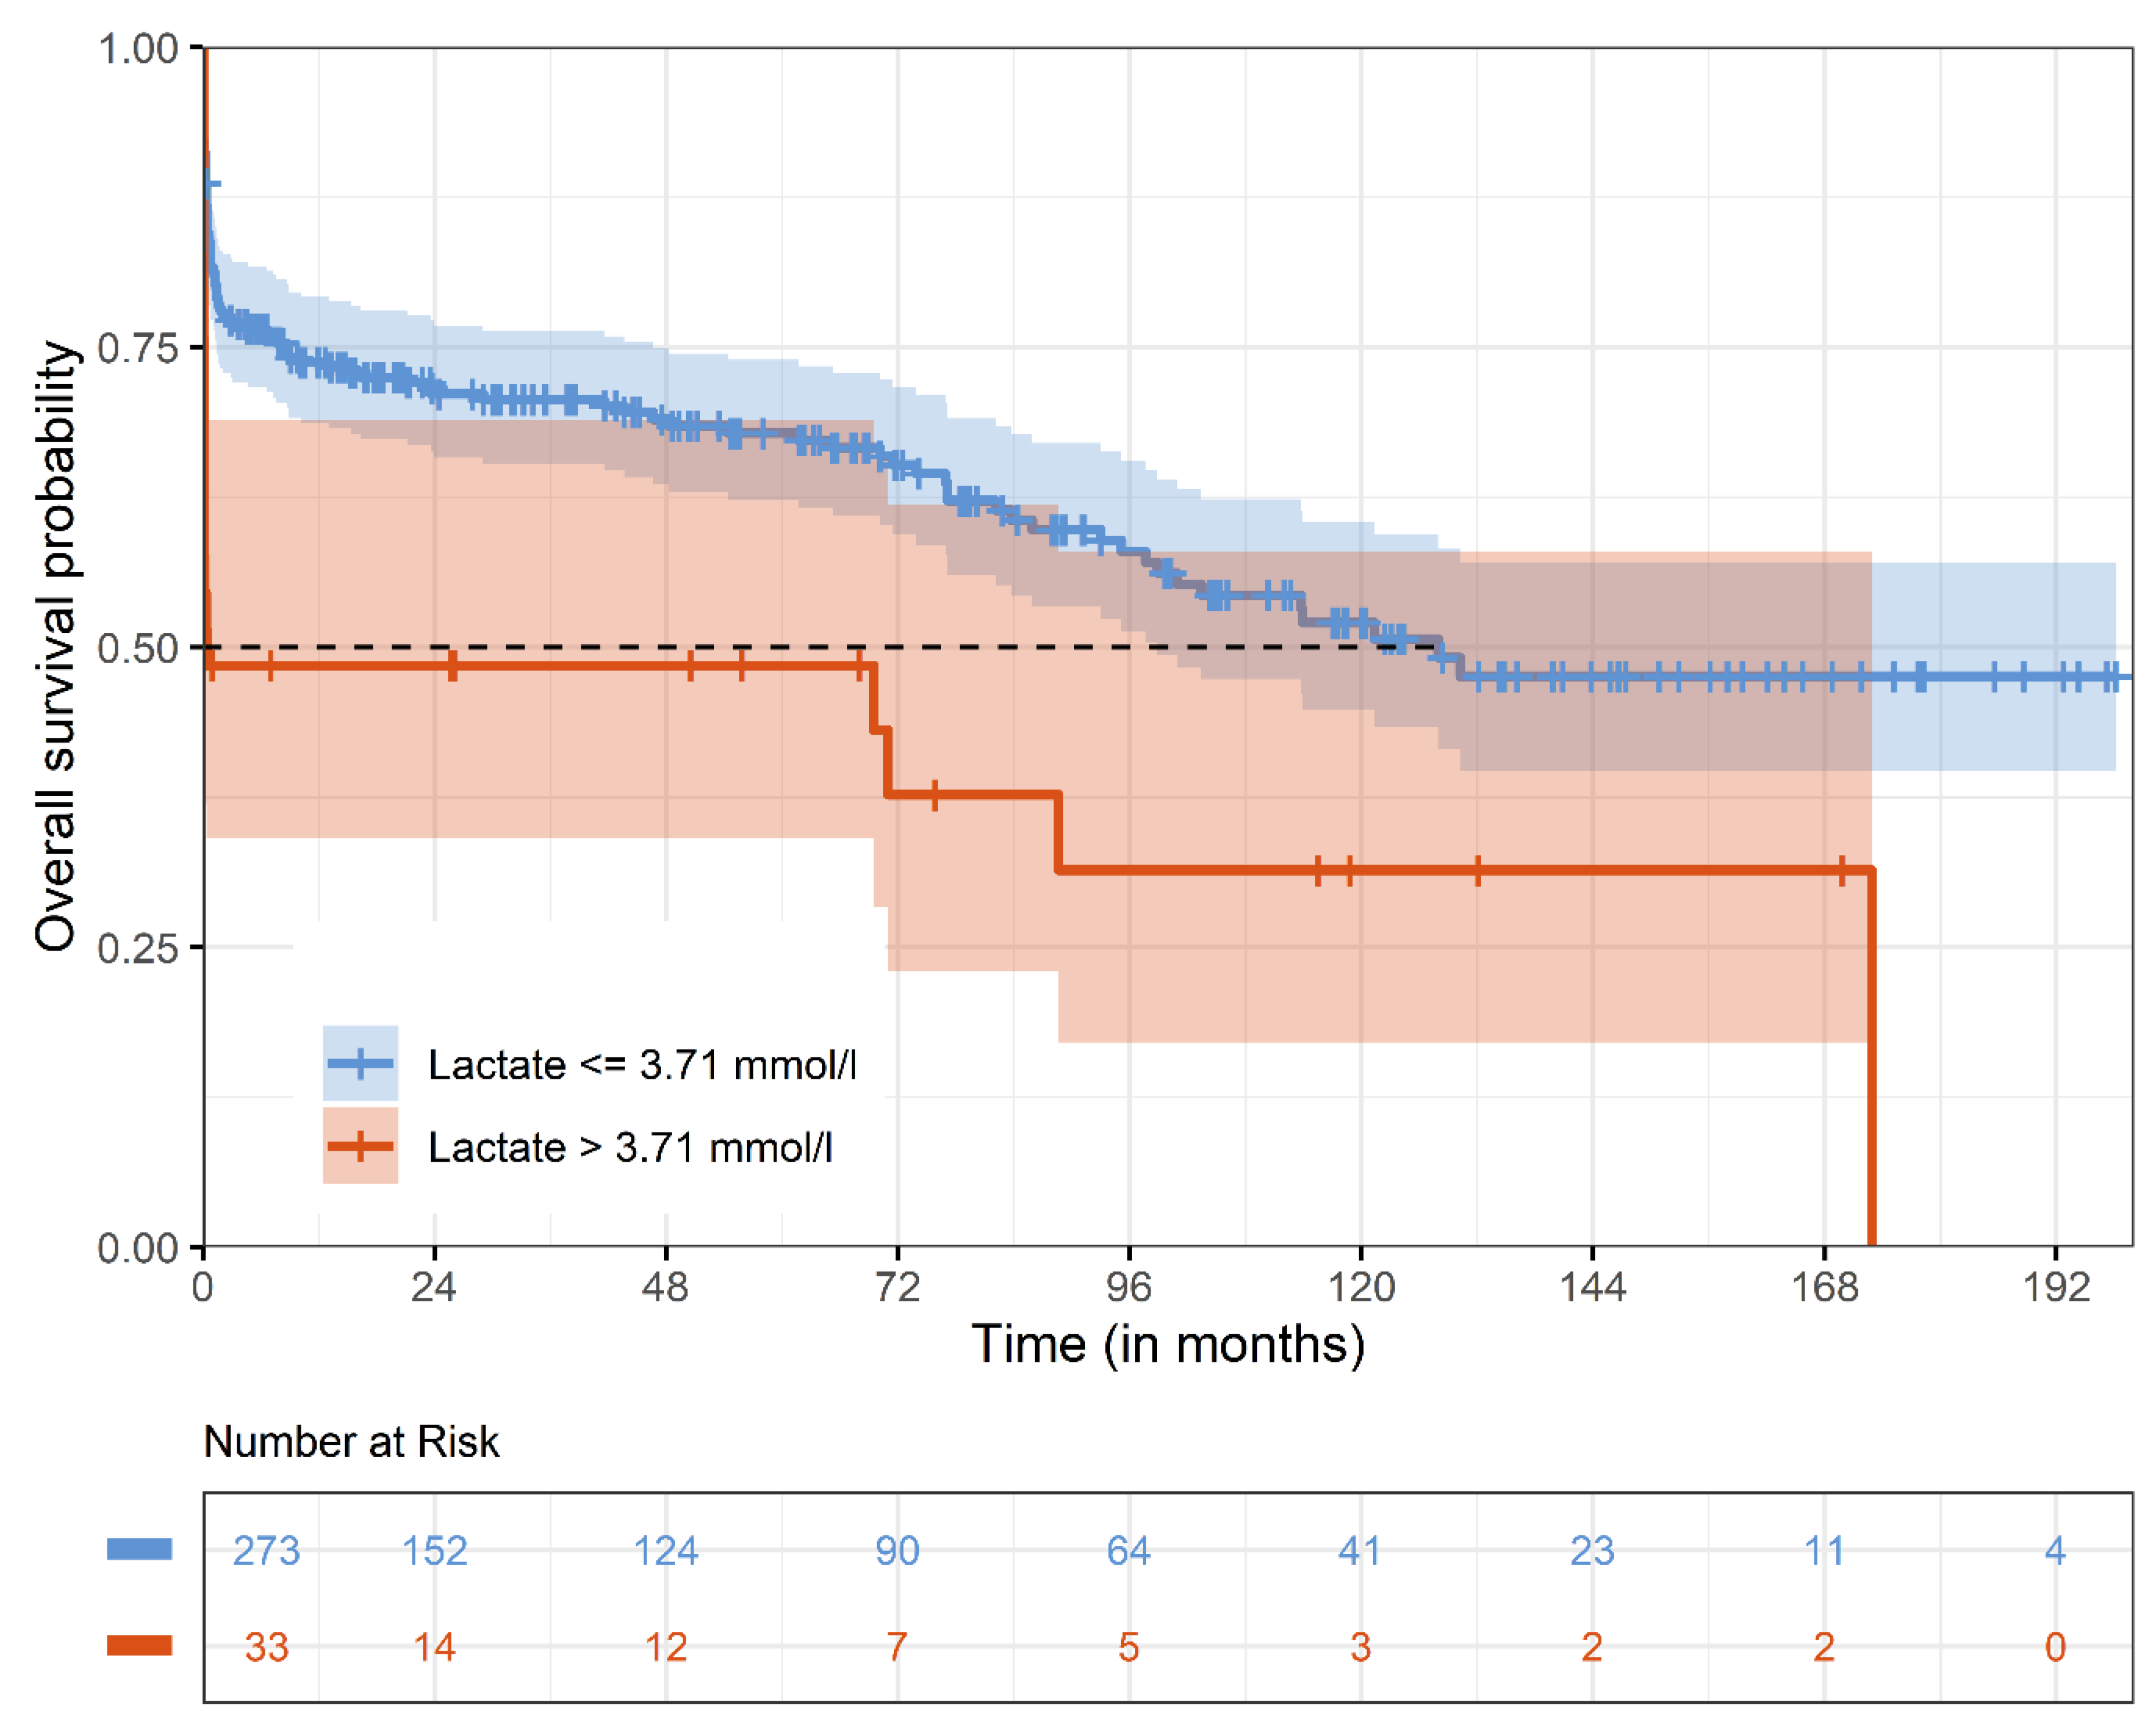
5. Thirty-Day Mortality and Survival
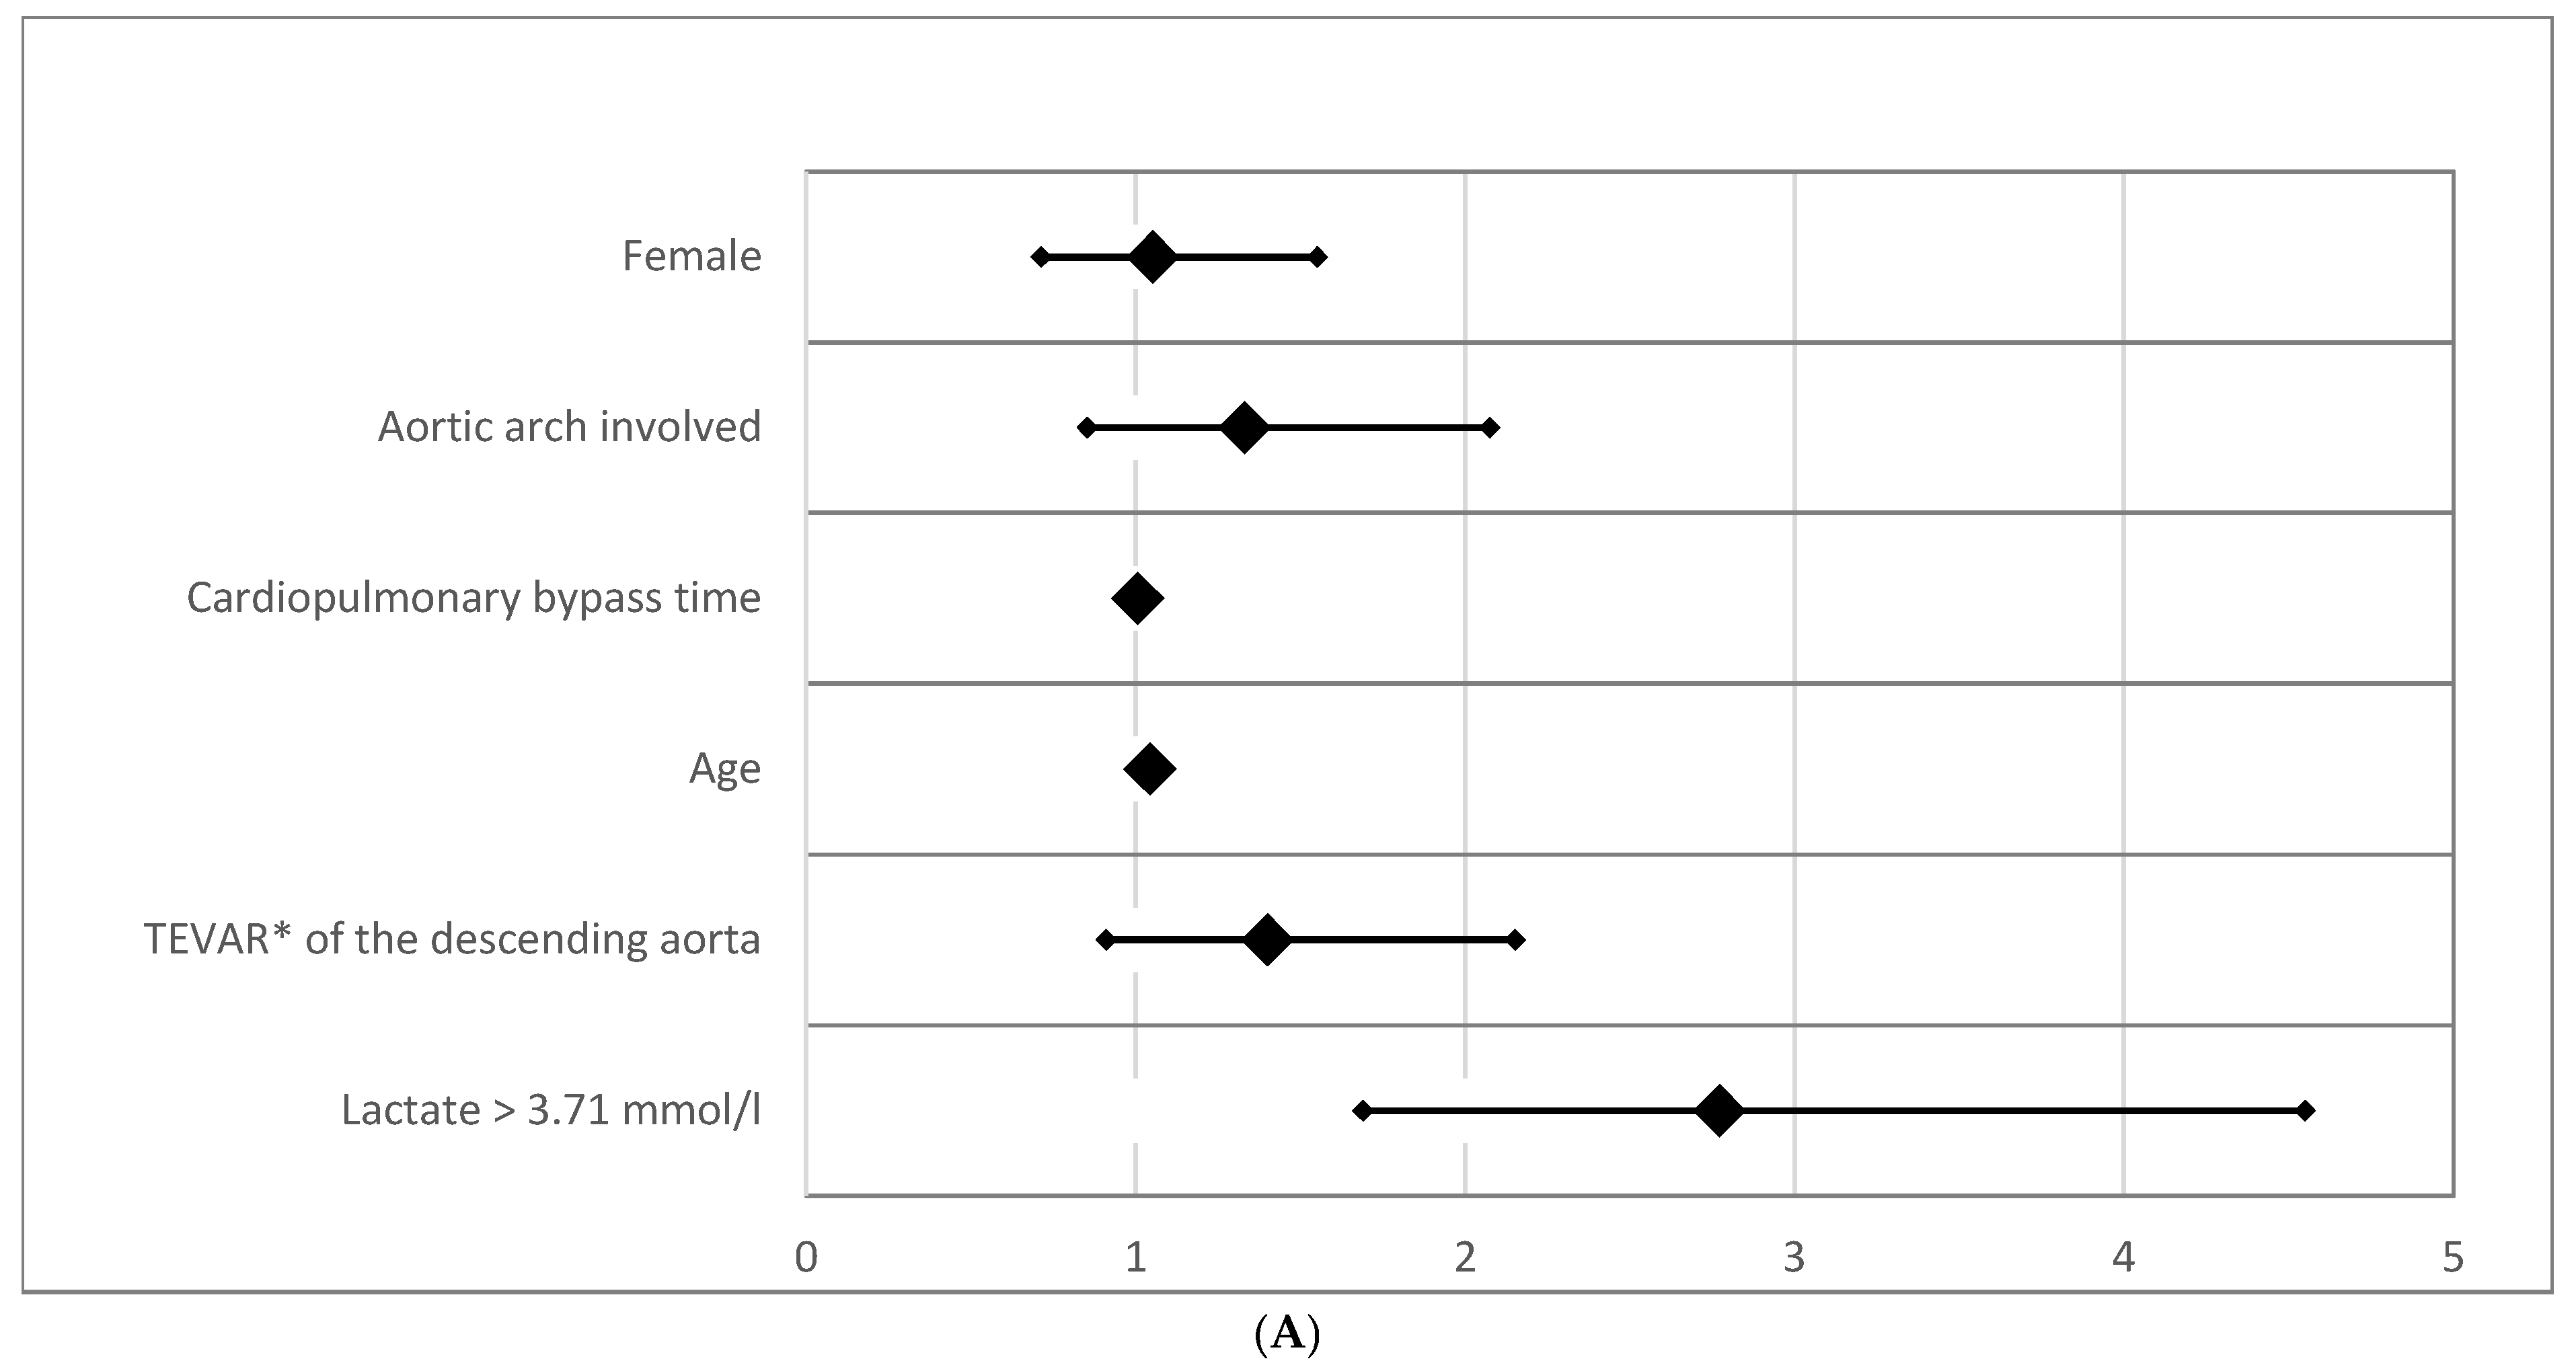
6. Risk Factor Analysis
7. Discussion
8. The Role of Organ Malperfusion
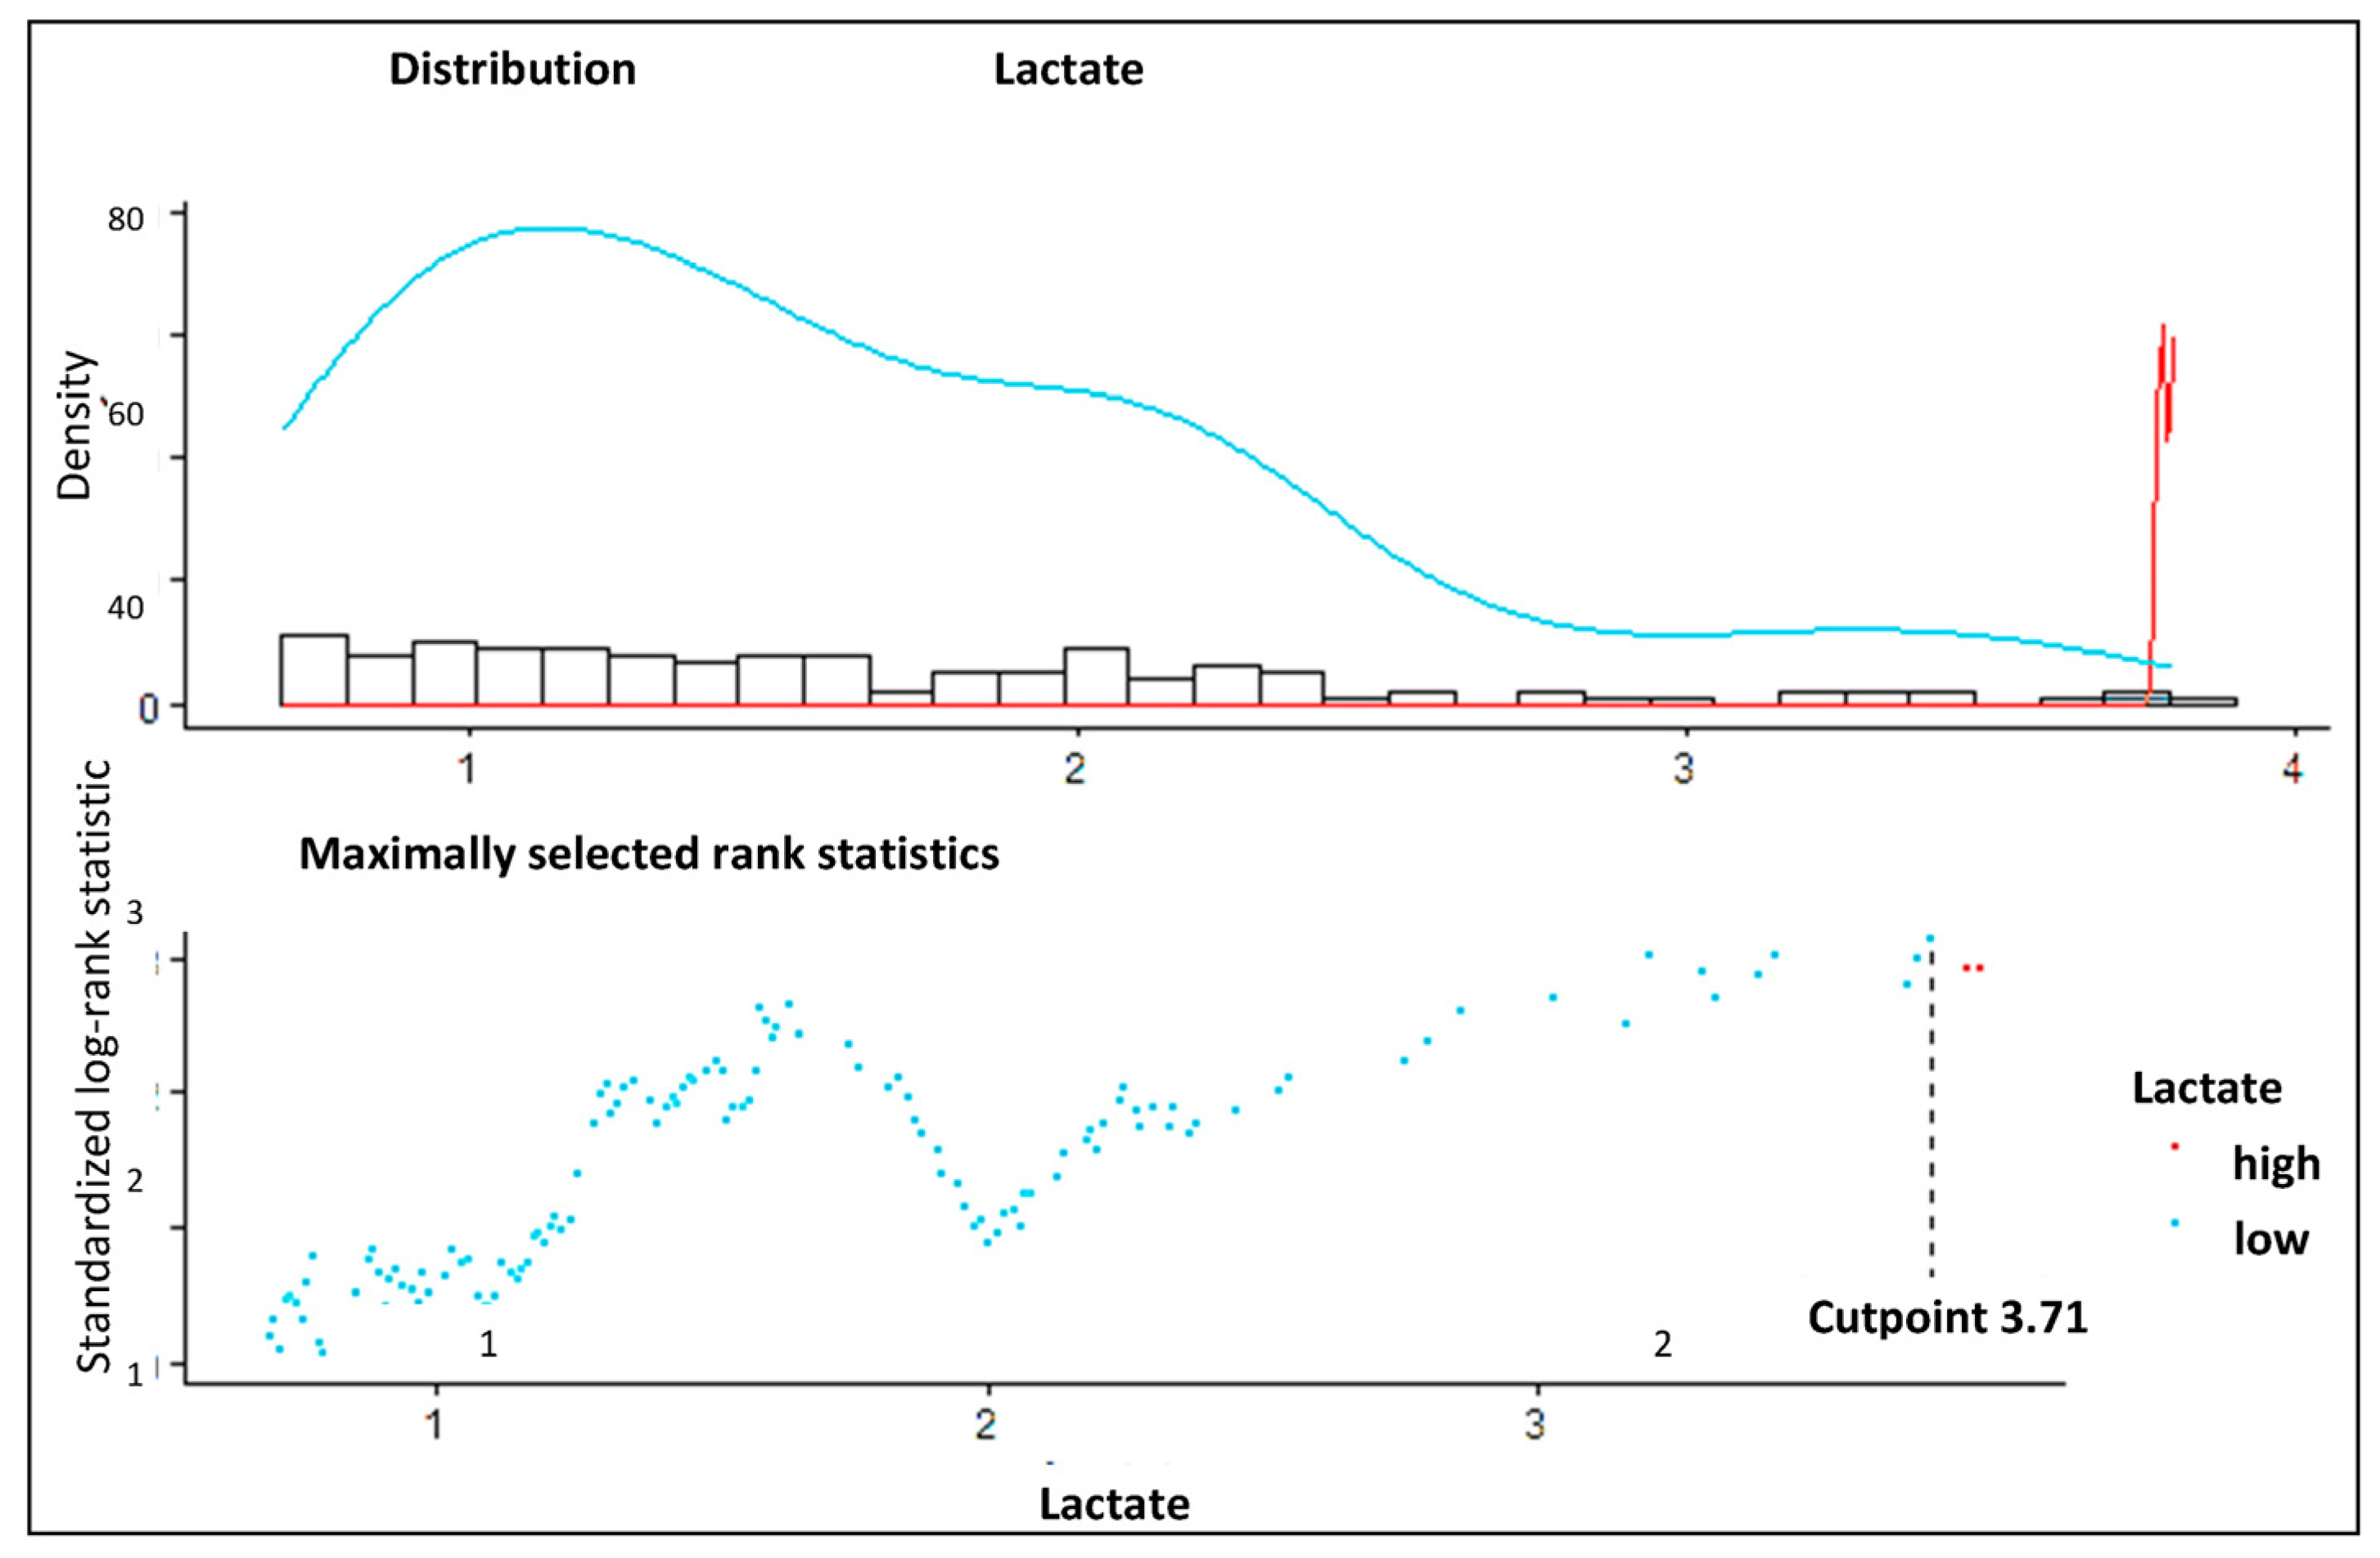
9. Cut-Off Level and the Prognostic Impact of Lactate Levels on Survival
10. Conclusions
11. Limitations
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
References
- Zhu, Y.; Lingala, B.; Baiocchi, M.; Tao, J.J.; Toro Arana, V.; Khoo, J.W.; Williams, K.M.; Traboulsi, A.A.R.; Hammond, H.C.; Lee, A.M.; et al. Type A Aortic Dissection—Experience over 5 Decades: JACC Historical Breakthroughs in Perspective. J. Am. Coll. Cardiol. 2020, 76, 1703–1713. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salem, M.; Friedrich, C.; Thiem, A.; Huenges, K.; Puehler, T.; Cremer, J.; Haneya, A. Risk Factors for Mortality in Acute Aortic Dissection Type A: A Centre Experience over 15 Years. Thorac. Cardiovasc. Surg. 2021, 69, 322–328. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Santini, F.; Montalbano, G.; Casali, G.; Messina, A.; Iafrancesco, M.; Luciani, G.B.; Rossi, A.; Mazzucco, A. Clinical Presentation Is the Main Predictor of In-Hospital Death for Patients with Acute Type A Aortic Dissection Admitted for Surgical Treatment: A 25 Years Experience. Int. J. Cardiol. 2007, 115, 305–311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mehta, R.H.; Suzuki, T.; Hagan, P.G.; Bossone, E.; Gilon, D.; Llovet, A.; Maroto, L.C.; Cooper, J.V.; Smith, D.E. Predicting Death in Patients with Acute Type A Aortic Dissection. Circulation 2002, 105, 200–206. [Google Scholar] [CrossRef] [Scilit]
- Czerny, M.; Schoenhoff, F.; Etz, C.; Englberger, L.; Khaladj, N.; Zierer, A.; Weigang, E.; Hoffmann, I.; Blettner, M.; Carrel, T.P. The Impact of Pre-Operative Malperfusion on Outcome in Acute Type A Aortic Dissection: Results from the GERAADA Registry. J. Am. Coll. Cardiol. 2015, 65, 2628–2635. [Google Scholar] [CrossRef] [Scilit]
- Suliman, A.; Dialynas, M.; Ashrafian, H.; Bicknell, C.; Mireskandari, M.; Hamady, M.; Athanasiou, T. Acute Complex Type A Dissection Associated with Peripheral Malperfusion Syndrome Treated with a Staged Approach Guided by Lactate Levels. J. Cardiothorac. Surg. 2010, 5, 4. [Google Scholar] [CrossRef] [Scilit]
- Li, Q.; Chen, L.; Shen, Y.; Li, J.; Dong, Y. A Modified Axillo-Femoral Perfusion for Acute Type A Aortic Dissection Accompanied with Lower Limb Malperfusion. J. Cardiothorac. Surg. 2020, 15, 10. [Google Scholar] [CrossRef] [Scilit]
- He, Q.; Tan, Z.; Chen, D.X.; Cai, S.; Zhou, L. Association between Intraoperative Hyperglycemia/Hyperlactatemia and Acute Kidney Injury Following On-Pump Cardiac Surgery: A Retrospective Cohort Study. Front. Cardiovasc. Med. 2023, 10, 1218127. [Google Scholar] [CrossRef] [Scilit]
- Zymliński, R.; Biegus, J.; Sokolski, M.; Siwołowski, P.; Nawrocka-Millward, S.; Todd, J.; Jankowska, E.A.; Banasiak, W.; Cotter, G.; Cleland, J.G.; et al. Increased Blood Lactate Is Prevalent and Identifies Poor Prognosis in Patients with Acute Heart Failure without Overt Peripheral Hypoperfusion. Eur. J. Heart Fail. 2018, 20, 1011–1018. [Google Scholar] [CrossRef] [Scilit]
- Muraki, S.; Fukada, J.; Morishita, K.; Kawaharada, N.; Abe, T. Acute Type A Aortic Dissection with Intestinal Ischemia Predicted by Serum Lactate Elevation. Ann. Thorac. Cardiovasc. Surg. 2003, 9, 79–80. [Google Scholar]
- R Core Team. R: A Language and Environment for Statistical Computing; R Foundation for Statistical Computing: Vienna, Austria, 2021; Available online: https://www.R-project.org/ (accessed on 10 May 2025).
- Hothorn, T. Maximally Selected Rank Statistics in R; 0.7-25. 2017. Available online: https://cran.r-project.org/web/packages/maxstat/index.html (accessed on 10 May 2025).
- Hothorn, T.; Hornik, K.; van de Wiel, M.A.; Zeileis, A. A Lego System for Conditional Inference. Am. Stat. 2006, 60, 257–263. [Google Scholar] [CrossRef] [Scilit]
- Kallenbach, K.; Berger, T.; Bürger, T.; Eggebrecht, H.; Harringer, W.; Helmberger, T.; Heringlake, M.; Karck, M.; von Kodolitsch, Y.; Schürholz, T.; et al. Guideline for the Treatment of Thoracic Aortic Dissection Type A: Summary of the S2k Guideline. Thorac. Cardiovasc. Surg. 2022, 70, 603–606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Augoustides, J.G.; Szeto, W.Y.; Desai, N.D.; Pochettino, A.; Cheung, A.T.; Savino, J.S.; Bavaria, J.E. Classification of Acute Type A Dissection: Focus on Clinical Presentation and Extent. Eur. J. Cardiothorac. Surg. 2011, 39, 519–522. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kramer, A.; Al Agha, S.; Böhm, L.; Michael, M.; Schulze-Bosse, K.; Bernhard, M. Lactate in Emergency Medicine. Anaesthesist 2020, 69, 826–834. [Google Scholar] [CrossRef] [Scilit]
- Yang, H.H.; Chang, J.C.; Jhan, J.Y.; Cheng, Y.T.; Huang, Y.T.; Chang, B.S.; Chao, S.F. Prognostic Value of Peak Lactate during Cardiopulmonary Bypass in Adult Cardiac Surgeries: A Retrospective Cohort Study. Tzu Chi Med. J. 2020, 32, 386–391. [Google Scholar] [CrossRef] [Scilit]
- Govender, P.; Tosh, W.; Burt, C.; Falter, F. Evaluation of Increase in Intraoperative Lactate Level as a Predictor of Outcome in Adults After Cardiac Surgery. J. Cardiothorac. Vasc. Anesth. 2020, 34, 877–884. [Google Scholar] [CrossRef] [Scilit]
- He, H.; Chai, X.; Zhou, Y.; Pan, X.; Yang, G. Association of Lactate Dehydrogenase with In-Hospital Mortality in Patients with Acute Aortic Dissection: A Retrospective Observational Study. Int. J. Hypertens. 2020, 2020, 1347165. [Google Scholar] [CrossRef] [Scilit]
- Luo, J.C.; Zhong, J.; Duan, W.X.; Tu, G.W.; Wang, C.S.; Sun, Y.X.; Li, J.; Lai, H.; Luo, Z. Early Risk Stratification of Acute Type A Aortic Dissection: Development and Validation of a Predictive Score. Cardiovasc. Diagn. Ther. 2020, 10, 1827–1838. [Google Scholar] [CrossRef] [Scilit]
- Demers, P.; Elkouri, S.; Martineau, R.; Couturier, A.; Cartier, R. Outcome with High Blood Lactate Levels During Cardiopulmonary Bypass in Adult Cardiac Operation. Ann. Thorac. Surg. 2000, 70, 2082–2086. [Google Scholar] [CrossRef] [Scilit]
- Bennett, J.M.; Wise, E.S.; Hocking, K.M.; Brophy, C.M.; Eagle, S.S. Hyperlactemia Predicts Surgical Mortality in Patients Presenting with Acute Stanford Type-A Aortic Dissection. J. Cardiothorac. Vasc. Anesth. 2017, 31, 54–60. [Google Scholar] [CrossRef] [Scilit]
- Sievers, H.H.; Rylski, B.; Czerny, M.; Baier, A.L.M.; Kreibich, M.; Siepe, M.; Beyersdorf, F. Aortic Dissection Reconsidered: Type, Entry Site, Malperfusion Classification Adding Clarity and Enabling Outcome Prediction. Interact. Cardiovasc. Thorac. Surg. 2020, 30, 451–457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Duval, B.; Besnard, T.; Mion, S.; Leuillet, S.; Jecker, O.; Labrousse, L.; Rémy, A.; Zaouter, C.; Ouattara, A. Intraoperative Changes in Blood Lactate Levels Are Associated with Worse Short-Term Outcomes after Cardiac Surgery with Cardiopulmonary Bypass. Perfusion 2019, 34, 640–650. [Google Scholar] [CrossRef] [Scilit] [PubMed]

| n = 306 | Mean ± SD or n (%) |
|---|---|
| Patient’s characteristics | |
| Age (years) | 59.44 ± 14.25 (18.12–92.16) |
| Female gender (n) | 95 (30.9%) |
| Marfan (n) | 13 (4.2%) |
| Lactate preoperative (mmol/L) | 1.95 ± 2.19 (0.15–19.27) |
| Lactate > 3.71 mml/L | 33 (10.7%) |
| Creatinine preoperative (mg/dL) | 1.13 ± 0.5 (0.39–5.68) |
| Elevated liver parameters (at admission; n) | 109 (35.5%) |
| Body mass index (BMI) (kg/m2) | 26.5 ± 4.0 |
| Left ventricular ejection fraction (%) | 62 ± 16.1 |
| Previous cardiac surgery (n) | 29 (9.4%) |
| Surgical and intraoperative data | |
| Surgery on the aortic arch (n) | 210 (68.4%) |
| SAVR * (n) | 111 (36.3%) |
| Bentall procedure (total; n) | 105 (34.2%) |
| Bentall procedure, mechanical SAVR (n) | 32 (10.5%) |
| David procedure (n) | 13 (4.2%) |
| TEVAR ** of the descending aorta | 84 (27.4%) |
| Concomitant CABG *** (n) | 54 (17.6%) |
| CPB **** time (minutes) | 195 ± 83 |
| Circulatory arrest (minutes) (n = 252; 82.4%) | 38.0 ± 29.9 |
| ECMO ***** (n; postoperative) | 7 (2.3%) |
| A | |||||
| B | Hazard Ratio (HR) | Lower Level (95% CI) | Upper Level (95% CI) | p-Value | |
| Lactate > 3.71 mmol/L | 1.020 | 2.772 | 1.689 | 4.550 | <0.0001 |
| TEVAR * of the descending aorta | 0.336 | 1.399 | 0.910 | 2.151 | 0.126 |
| Age | 0.042 | 1.043 | 1.026 | 1.059 | <0.0001 |
| Cardiopulmonary bypass time | 0.006 | 1.006 | 1.004 | 1.008 | <0.0001 |
| Aortic arch surgery | 0.285 | 1.330 | 0.853 | 2.074 | 0.208 |
| Female gender | 0.050 | 1.051 | 0.713 | 1.551 | 0.800 |
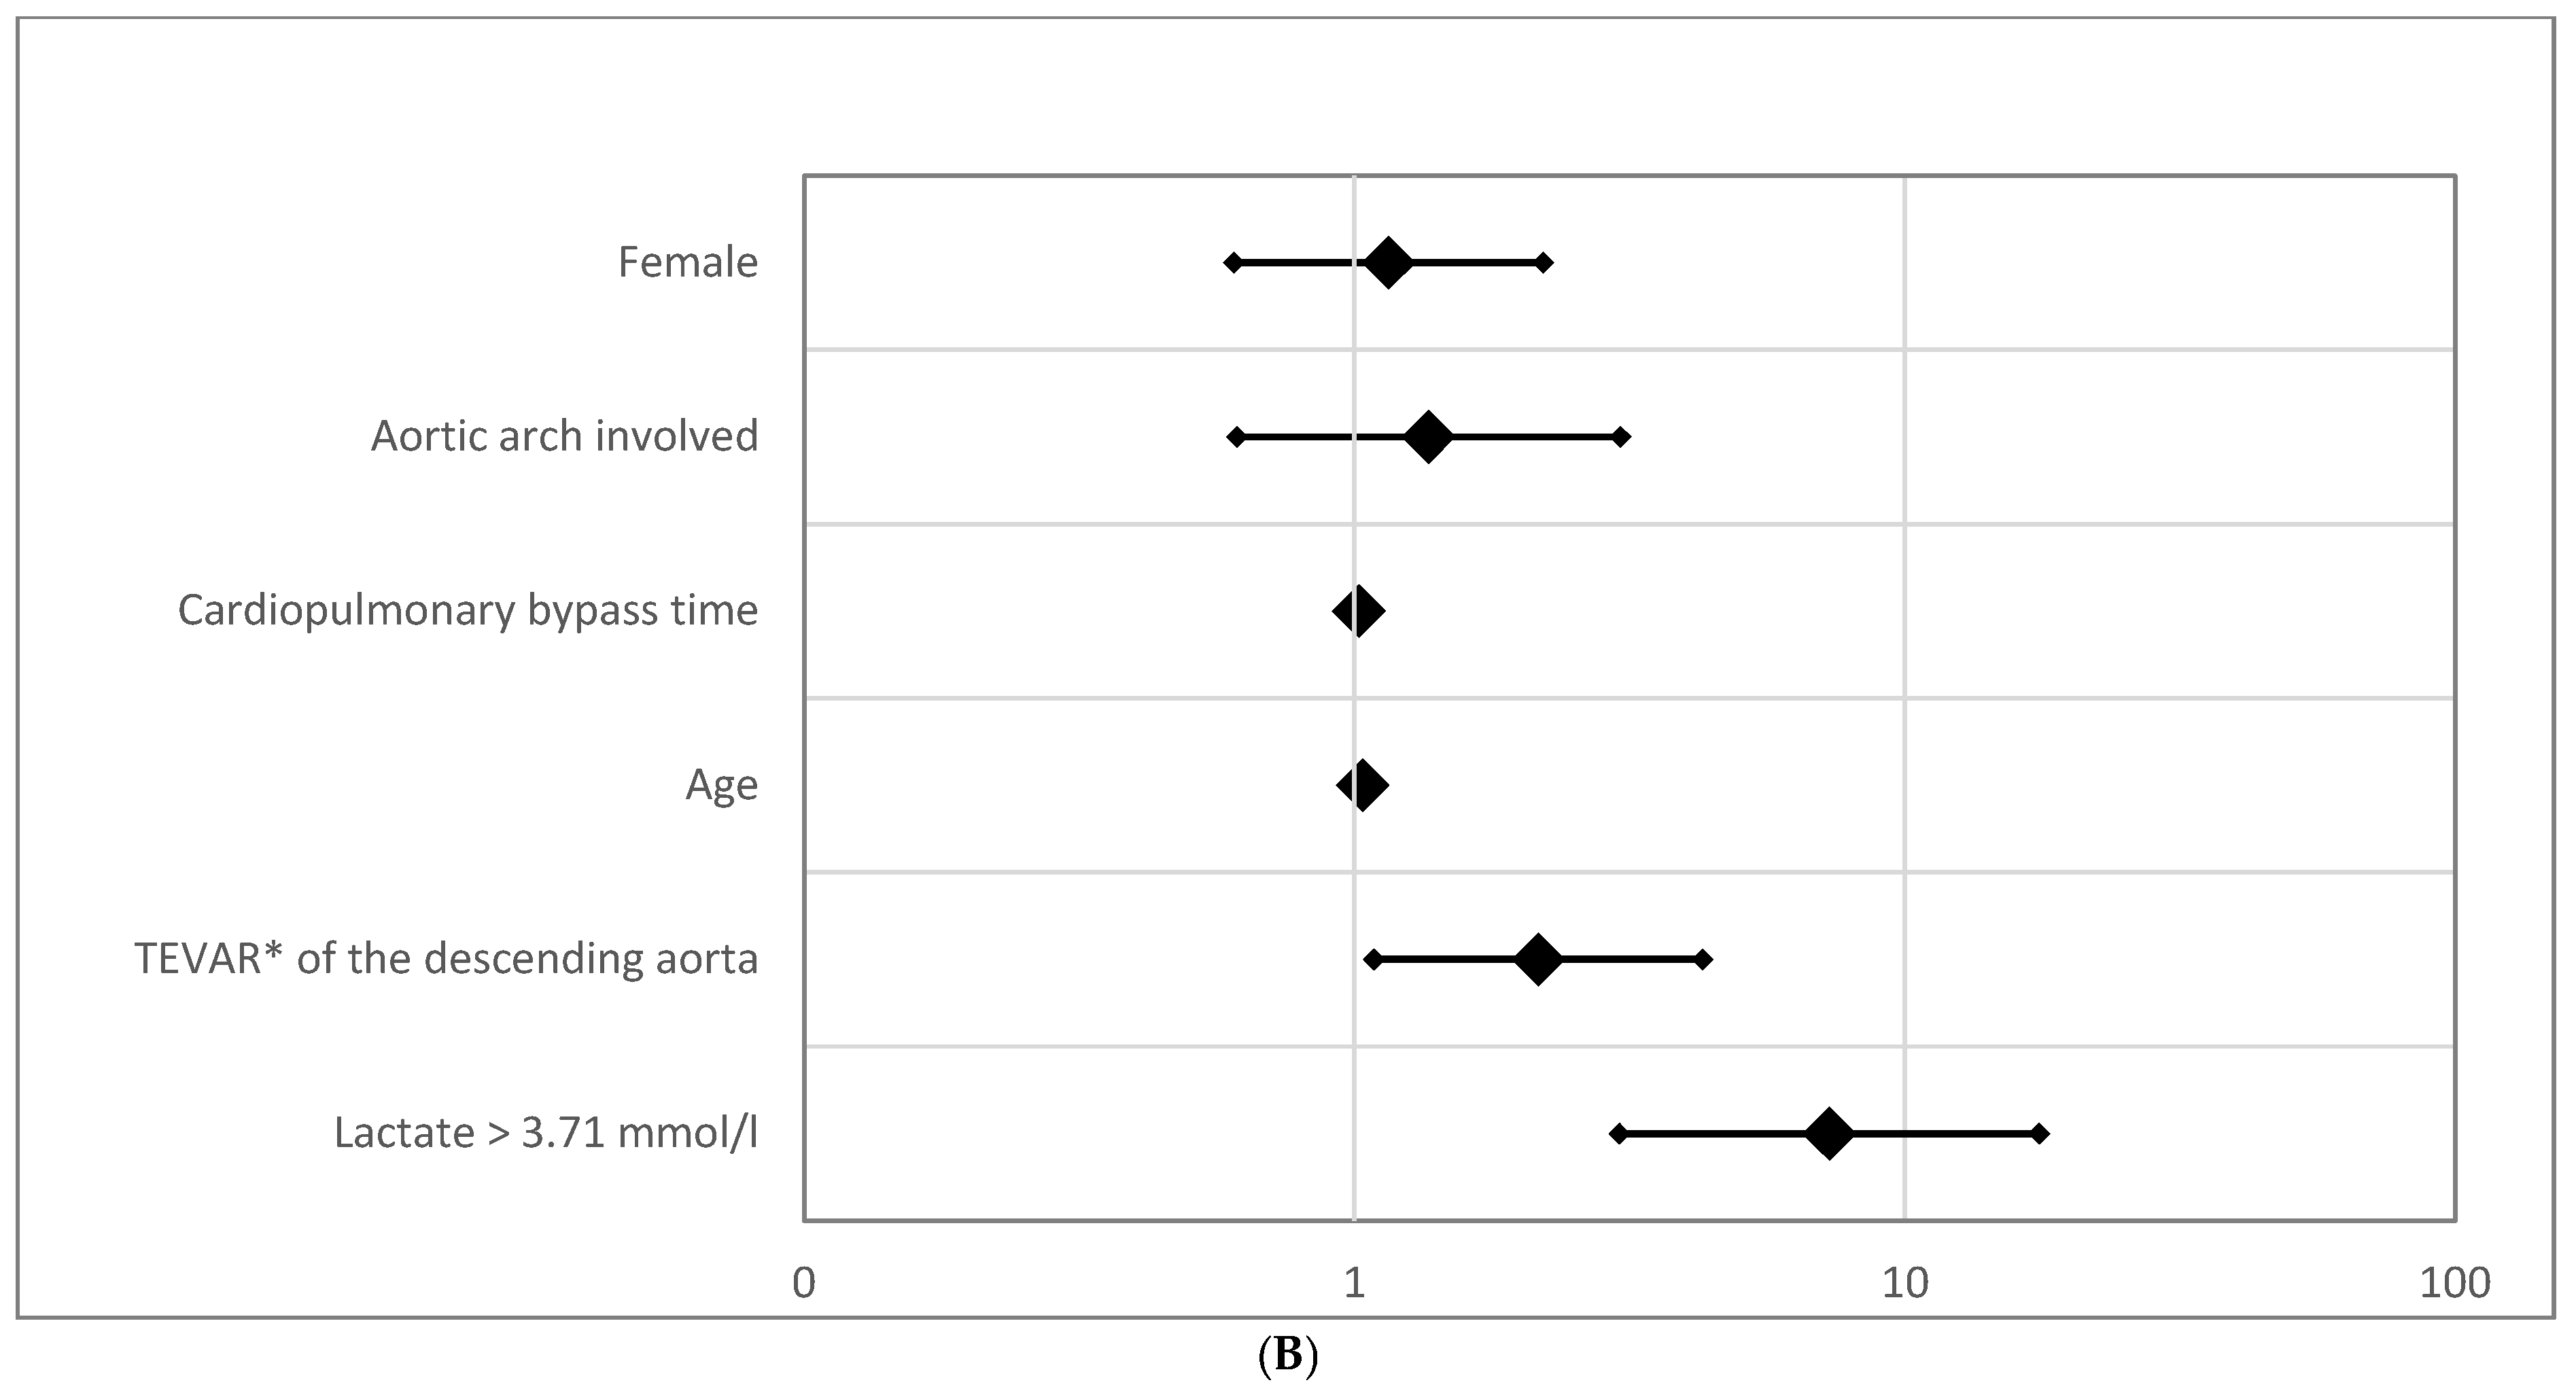
| B | |||||
| B | Odds Ratio (OR) | Lower Level (95% CI) | Upper Level (95% CI) | p-Value | |
| Lactate > 3.71 mmol/L | 1.987 | 7.292 | 3.029 | 17.555 | <0.0001 |
| TEVAR * of the descending aorta | 0.769 | 2.158 | 1.085 | 4.291 | 0.028 |
| Age | 0.035 | 1.036 | 1.010 | 1.062 | 0.006 |
| Cardiopulmonary bypass time | 0.009 | 1.009 | 1.005 | 1.013 | <0.0001 |
| Aortic arch involved | 0.311 | 1.365 | 0.612 | 3.044 | 0.447 |
| Female gender | 0.172 | 1.187 | 0.620 | 2.275 | 0.605 |
| Constant | −6.096 | 0.002 | <0.0001 | ||
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).
Share and Cite
Puluca, N.; König, C.; Wiesner, G.; Waschulzik, B.; Vitanova, K.; Krane, M.; Böhm, J. Preoperative Hyperlactatemia Predicts Mortality in Acute Stanford Type A Dissection: A 16-Year-Period, Single-Center, Retrospective Study. J. Clin. Med. 2025, 14, 3619. https://doi.org/10.3390/jcm14113619
Puluca N, König C, Wiesner G, Waschulzik B, Vitanova K, Krane M, Böhm J. Preoperative Hyperlactatemia Predicts Mortality in Acute Stanford Type A Dissection: A 16-Year-Period, Single-Center, Retrospective Study. Journal of Clinical Medicine. 2025; 14(11):3619. https://doi.org/10.3390/jcm14113619
Chicago/Turabian StylePuluca, Nazan, Christian König, Gunther Wiesner, Birgit Waschulzik, Keti Vitanova, Markus Krane, and Johannes Böhm. 2025. "Preoperative Hyperlactatemia Predicts Mortality in Acute Stanford Type A Dissection: A 16-Year-Period, Single-Center, Retrospective Study" Journal of Clinical Medicine 14, no. 11: 3619. https://doi.org/10.3390/jcm14113619
APA StylePuluca, N., König, C., Wiesner, G., Waschulzik, B., Vitanova, K., Krane, M., & Böhm, J. (2025). Preoperative Hyperlactatemia Predicts Mortality in Acute Stanford Type A Dissection: A 16-Year-Period, Single-Center, Retrospective Study. Journal of Clinical Medicine, 14(11), 3619. https://doi.org/10.3390/jcm14113619



