


Abstract
Schizophrenia is a psychiatric disorder that makes patients incompetent to perform day-to-day activities due to their progressing mental illness. In addition to disturbances with thoughts, behavioral changes, and impaired cognitive functions, oro-systemic health also becomes compromised. Even though the population with schizophrenia is primarily made up of older people, little is known about this group’s oral health treatment. The present review explores the relationship between oral healthcare and elderly patients with schizophrenia. Our literature search included databases, like PubMed, Embase, and Google Scholar, for appropriate and evidence-based information. Preventive and management strategies outlined in the included articles and future research perspectives in this field are discussed. To the best of our knowledge, this is the first review that looked at dental care and related characteristics in older schizophrenia patients. The findings highlight the necessity for targeted dental interventions to address the dental health challenges faced by this vulnerable population. Integrating dental health into the overall medical management of elderly individuals with schizophrenia is crucial. Although specific therapies remain limited, the emphasis is on preventive dentistry to reduce the occurrence and progression of oral diseases in this group.
1. Introduction
Schizophrenia is a chronic heterogenous psychological disorder whose symptoms include, but are not limited to, delusion and hallucination (positive symptoms), apathy, social withdrawal, anhedonia (negative symptoms), and cognitive deficits [1]. The description of schizophrenia has evolved through the years. The definition and boundaries have changed; however, its etiology and pathophysiology remain elusive. The International Classification of Diseases-11 (ICD-11) describes schizophrenia and other primary psychotic disorders by characteristics, such as significant impairments testing and alterations in behavior manifest in positive symptoms, such as persistent delusions, persistent hallucinations, disorganized thinking (typically manifest as disorganized speech), grossly disorganized behavior, and experiences of passivity and control, negative symptoms, such as blunted or flat affect and avolition, and psychomotor disturbances. The symptoms occur with sufficient frequency and intensity to deviate from expected cultural or subcultural norms. They do not arise as a feature of another mental and behavioral disorder (e.g., a mood disorder, delirium, or a disorder due to substance use). The categories in this grouping should not be used to classify the expression of ideas or beliefs, or be culturally sanctioned [2]. Most of the patient population continues to face challenges concerning occupational and social functioning [3]. Even though the population with schizophrenia is primarily made up of older people, little is known about this group’s oral health treatment. According to several authors, patients with schizophrenia do not always receive the best oral health treatment [4,5,6,7]. They are believed to be more vulnerable to developing dental diseases due to their decreased capacity for planning, lack of motivation, difficulty performing oral hygiene tasks, challenges they encounter by being refused treatment on the grounds of inability to maintain oral hygiene, and their increased propensity to experience adverse orofacial effects, such as xerostomia, sialorrhea, and oral dyskinesia brought on by psychotropic medications. Aside from age, one study found that gender, education, and minority status were not connected with dental care in older persons and were not relevant in schizophrenia [8]. On the other hand, due to the lengthy wait times and feelings of stigma, patients do not seek dental care with Medicaid, the public healthcare system in the United States [8]. To the best of our knowledge, this is the first review that looked at dental care and related characteristics in older schizophrenia patients. The aim of this narrative review is to provide an overview of the available literature on the correlation between geriatric patients diagnosed with schizophrenia and their oral health status.
2. Materials and Methods
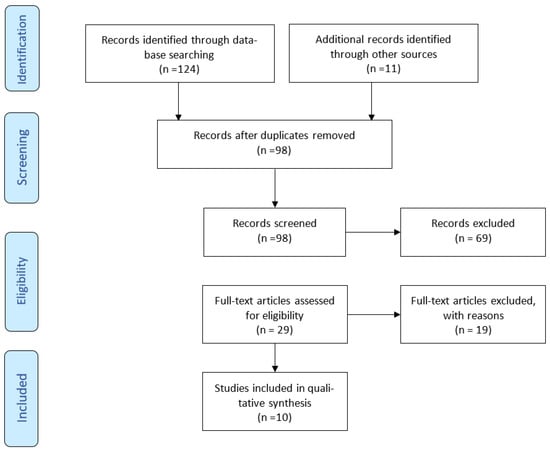
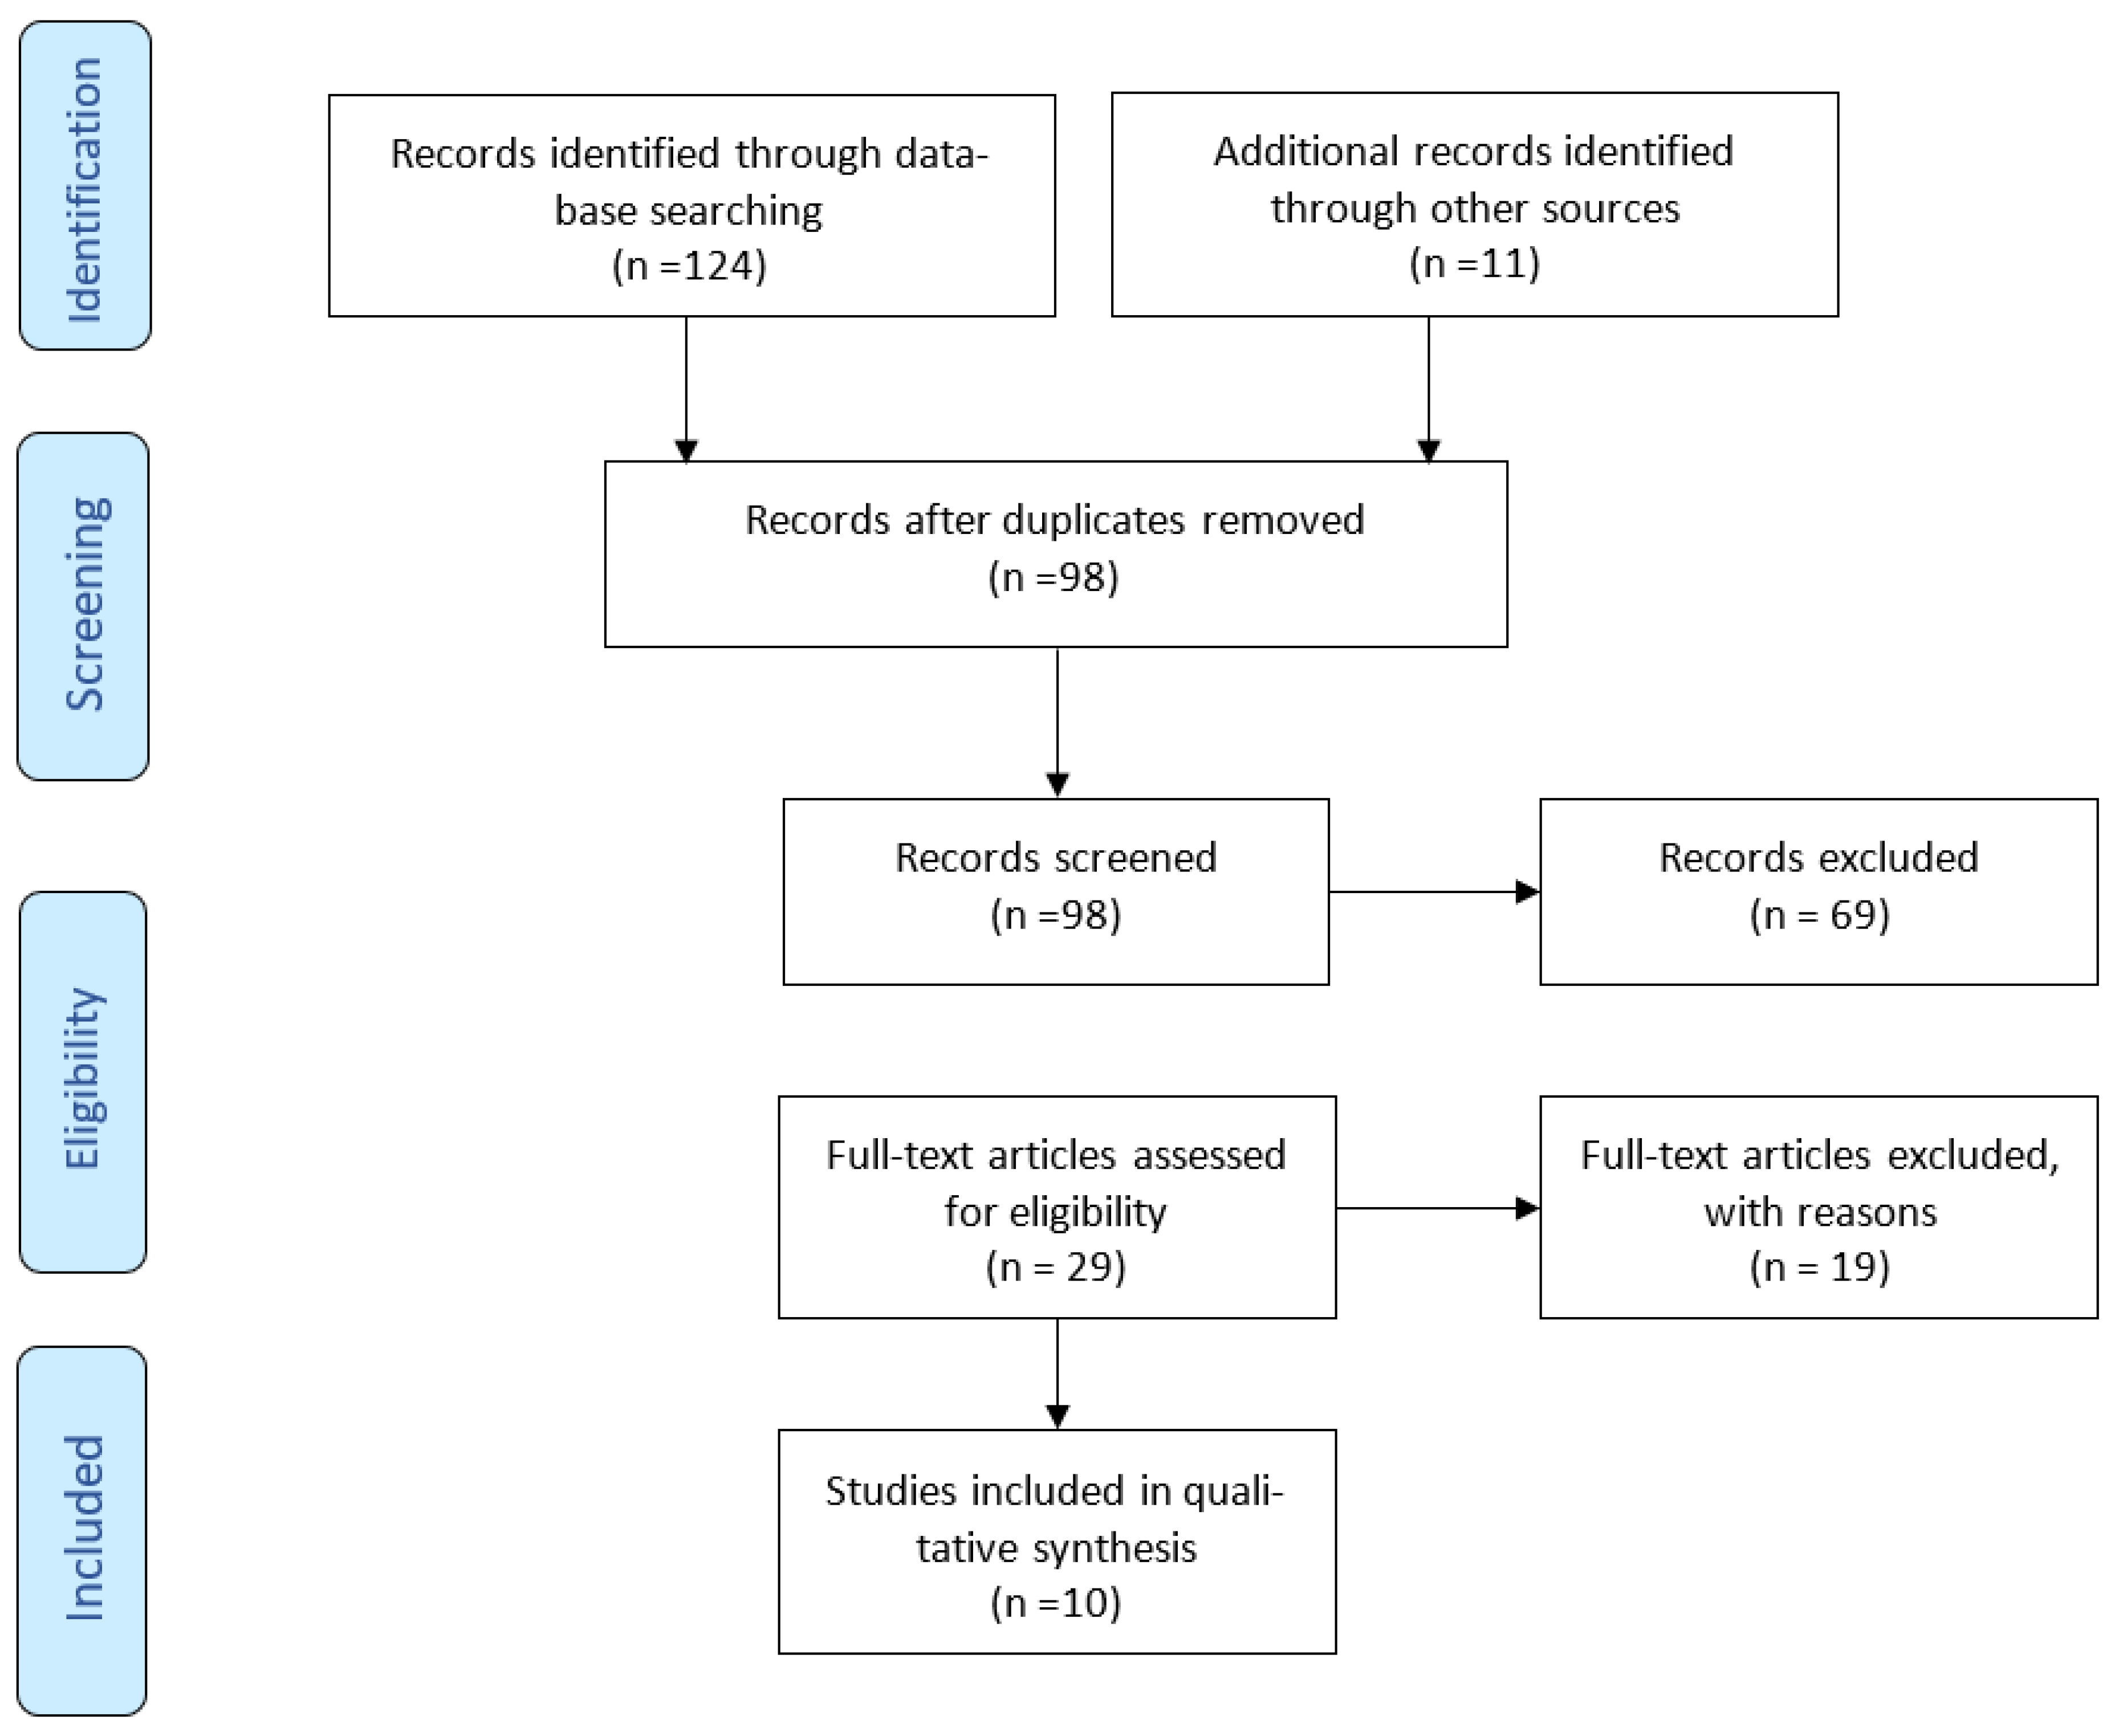
We conducted a literature review in the online electronic databases PubMed, Embase, and Google Scholar by searching for appropriate and evidence-based information. Our search strategy includes the keywords “Schizophrenia, Oral Care, Oral Health, Dental Care for Aged, Geriatric Dentistry, and Elderly”. Overall, 124 articles were found, and after removing duplicates and excluding articles based on our research question, 10 full-text articles were included in our review. The inclusion criteria were (i) original studies and (ii) schizophrenic patients older than 50 years old. Excluded were (i) review articles, (ii) schizophrenic patients less than 50 years old, and (iii) studies that categorized schizophrenic patients along with other mentally disordered patients in general (Figure 1).
Figure 1.
A flow diagram of the search strategy conducted (PRISMA flow of study selection process).
3. Results
Table 1 discusses the literature showing oral health status in older adults with schizophrenia. It illustrates that older schizophrenia patients encounter higher oral health concerns, such as increased dental caries and poor periodontal health, as a result of medication-induced issues or inaccessibility to routine dental care. The table summarizes various studies conducted on the oral health of individuals with psychiatric disorders, particularly schizophrenia. Kurokawa et al. [9] conducted a cross-sectional study involving hospitalized patients with schizophrenia and found that older male patients with poor activities of daily living and low self-oral hygiene abilities exhibited poor oral hygiene. Joanna Ngo et al. [10] also conducted a cross-sectional study and discovered that male patients and older individuals had higher caries experience, with dry mouth being associated with typical antipsychotics. Zusman et al. [11] revealed in their cross-sectional study that the highest DMFT score was found in the older age group, emphasizing the need for improved dental care for chronic psychiatric patients. Denis et al. [12] conducted a qualitative study and highlighted the oral symptoms experienced by individuals with psychiatric disorders and the need for better oral hygiene support. Grinshpoon et al. [13] observed that patients taking atypical antipsychotics had better dental health than those on typical ones. Janarthanan et al. [9] emphasized the importance of targeting individuals with financial and cognitive difficulties for dental care. Chek Wey et al. [14] found poor oral hygiene and side effects of psychotropic medications among psychiatric patients, calling for preventive care. Tani et al. [15] revealed that older age, smoking, and less frequent tooth brushing were negatively related to dental conditions in schizophrenia patients. Kuan-Yu Chuet al. [16,17] identified various factors, including age, medication, and institutional stays, that influenced dental health in patients with schizophrenia. These studies collectively highlight the need for improved dental care and preventive strategies for individuals with schizophrenia, especially those who are older or facing challenges in their daily activities.
Table 1.
Literature shows oral health status in older adults with schizophrenia.
4. Discussion
4.1. Relationship between Etiology of Schizophrenia and Oral Health
Understanding and maintaining good dental health might be difficult for those with schizophrenia. There is evidence that mental health is connected to oral health and that they share a bidirectional relationship [18]. Dental problems frequently observed among psychiatric patients include periodontal disease and dental caries [19]. This is primarily because oral health is not emphasized in the setting of mental illness [20]. Periodontal disease and its progression may be negatively impacted by changes in inflammatory-related genes, genetic polymorphism of cytokines, and proinflammatory cytokine dysregulation in schizophrenia patients, which includes an elevation in levels of IL-1, IL-6, IL-9, TNF α, TNF β, PGE2, and CRP [21,22]. Mental disorders may also cause dysregulation of the hypothalamic–pituitary–adrenal and sympathoadrenal medullary axes. When these axes are dysregulated, a cascade of inflammatory, neurotransmitter, and hormonal mediators occurs [23]. As a result, an imbalance in the oral microbiome is created, causing decreased immunological function, altered salivary phenotype, and bruxism, all of which increase the likelihood of developing a variety of oral disorders, including dental caries, periodontal diseases, and tooth wear [24,25]. On the other hand, neuroinflammation in schizophrenic patients can also occur at advanced stages of periodontal diseases or oral abscesses when oral bacteria and/or their toxins invade the blood and/or cranial nerves [26].
4.2. Oral Manifestations
The aging process is linked to physical and sensory impairments causing inadequate oral health care. Adding the devastating effects of this psychiatric disorder has the potential to deteriorate their oral health further. Schizophrenia is characterized by impairing the subject’s capacity to carry out oral hygiene effectively, leading to a greater likelihood of experiencing poor oral health [6,13]. Research findings indicate that a significant proportion, ranging from 61% to 83% of individuals diagnosed with schizophrenia, experience dental disease [27]. The severity of the diagnosis, sex, social history, medications, and whether the patient is institutionalized or not play a role in oral health outcomes [6,9,10,13,28].
4.2.1. Dental Caries
Most studies assess caries experience by utilizing DMFT scores. However, a limitation of this scoring system is that it not only reflects the impact of the disease but also considers the individual’s lifetime history of caries. Nevertheless, patients with schizophrenia have been associated with higher scores when compared to patients with other mental disorders [11]. A study conducted on 1108 institutionalized residents with schizophrenia concluded that age was a significant factor related to a high level of dental caries [16]. Other studies on this population have revealed that males tend to exhibit higher DMFT scores than females. This is attributed to factors, such as a history of smoking, being first-time visitors to a dental clinic, or negligence of dental care [9,10,28].
4.2.2. Deficient Oral Hygiene
Individuals with schizophrenia often struggle with a lack of motivation, which can hinder their ability to maintain regular oral hygiene practices. These characteristics have been demonstrated in patients with severe negative symptoms and certain personality disorders [15,28]. Additionally, anxiety surrounding dental treatment may cause hesitation in seeking timely dental care. Consequently, this delay in seeking treatment can lead to the need for more complex and costly dental interventions or even losing dentition, further contributing to the individual’s anxiety. As previously mentioned, antipsychotic medications can impact fine motor skills. Tremors, in particular, can make it challenging for individuals to hold a toothbrush and properly perform flossing effectively. It has been found that a greater degree of tremor has been associated with a greater DMFT [15].
4.2.3. Xerostomia
The use of antipsychotics and anticholinergics causes salivary gland hypofunction and xerostomia, which increases the incidence of dental caries. Due to experiencing dry mouth, individuals tend to consume sugary drinks more frequently, thereby exacerbating the chance of tooth decay [13,28,29,30]. The decrease in salivary flow among patients with schizophrenia results in a diminished buffering capacity, increasing the likelihood of an acidic oral environment promoting the demineralization of tooth enamel and increasing the rapid progression of decay [13,28,29,30].
4.2.4. Effects of Tobacco
According to Winterer, individuals diagnosed with schizophrenia have a higher prevalence of smoking than patients with other mental disorders, with rates ranging from approximately 70% to 80%. It has been observed that smoking can have potential benefits for patients with schizophrenia, particularly in alleviating negative and cognitive symptoms [6,31]. This positive impact is believed to occur through the release of dopamine and stimulation of its activity, as well as the inhibition of its degradation [6,31]. Nevertheless, smoking has been positively associated with higher DMFT in several studies [13,28,29,30]. This fact has been consistent across samples in the literature. It is widely recognized that smoking not only contributes to an increase in pocket depths, loss of attachment, and loss of teeth affecting overall health, but it also increases the risk of developing oral cancer [15]. It is vital to promote smoking cessation programs in the dental office and perform oral cancer screenings routinely.
4.2.5. Temporomandibular Disorders
Recent studies show that temporomandibular disorders are more prevalent after childbearing age (45–64) and gradually decrease as age advances. In older adults, TMD is self-limiting and can be treated [32]. Interestingly, in older patients with schizophrenia, these orofacial disorders are frequently observed due to the long-term use of antipsychotic medications and the comorbid conditions associated with the disease. These individuals may exhibit reduced sensitivity to somatic pain, resulting in delayed consultation and further joint deterioration [33]. The combination of masticatory muscle tension, clenching, grinding, and emotional distress places them at a heightened risk of developing temporomandibular disorders (TMD). A study by Gurbuz et al. reported a prevalence of any sign of TMD in 87% of patients with schizophrenia, and 39.2% of these patients exhibited severe tooth wear [33]. The reported percentages highlight a potential connection between these two conditions, raising the need for dental providers to assess and manage TMD, ensuring comprehensive oral care for this population.
4.2.6. Tardive Dyskinesia
This adverse effect of antipsychotics causes involuntary movements of the extremities, trunk, and orofacial movements manifested as lip smacking, tongue protrusion, grinding mandibular movements, and puckering. These involuntary mandible movements can affect teeth and occlusion [13,34]. Individuals aged 60 and above are particularly vulnerable to the effects of medications. The progression of the disease is influenced by factors, such as the dosage and potency of the antipsychotics [34].
4.3. Dental Management
Dental treatment becomes difficult in this population due to several factors. There needs to be more communication between the dental provider and the patient. Cognitive impairments and disorganized thinking might hinder effective communication during dental visits, making understanding and addressing patients’ needs challenging. Having a caregiver present during dental visits can indeed be beneficial in managing the challenges associated with treating individuals with schizophrenia. Caregivers can provide support, help with communication, and assist in addressing the specific needs and concerns of the patient. They can also help promote oral hygiene practices and ensure adherence to dental care recommendations outside the dental office. The presence of a caregiver can enhance the whole dental experience for the patient and facilitate effective communication and cooperation between the dentist, patient, and caregiver.
Dental anxiety, agitation, or aggression is frequent in these patients. In some cases, dental procedures must be performed under nitrous oxide or sedation, which require special training, making the procedure more expensive for the patient. This limits the availability of specialized dental services for these individuals or a dentist willing to see them.
A study conducted by Zusman et al., reported that they observed a high number of extracted teeth (19 per patient, with one-third of the patients missing 26–32 teeth) due to caries and failure to restore them. They encourage dentists to work on preventive strategies to avoid extractions or complex procedures to preserve the natural dentition in this population [11].
The incorporation of fluoride applications during routine dental visits and prescriptions of high-fluoride toothpaste aid in countering the heightened susceptibility to dental caries often observed in this population. Complementing this, the utilization of specialized oral hygiene devices, tailored to accommodate potential motor and cognitive limitations [11], can facilitate effective plaque removal and maintenance of oral hygiene. Regular and frequent dental cleanings serve as a cornerstone of preventive care [11], enabling timely identification and management of dental issues. In addition, imparting nutrition education that emphasizes a reduction in sugar consumption [11] contributes significantly to oral health improvement [11]. Given the propensity for unhealthy dietary habits, such guidance can empower individuals with schizophrenia to make informed dietary choices that mitigate the risk of dental problems [11] These multifaceted preventive strategies, encompassing fluoride toothpaste, tailored oral hygiene devices, frequent cleanings, and nutritional education, collectively strive to address the intricate oral health needs of schizophrenia patients, enhancing their overall health outcomes.
According to a study by Grinshpoon et al., patients treated with atypical antipsychotics demonstrated better dental health than those taking typical antipsychotics [13]. This improvement is attributed to the reduced extrapyramidal effects associated with atypical antipsychotics, facilitating better medication adherence. As a result, symptom management is enhanced, leading to an improved quality of life and increased adherence to oral health regimes resulting in better oral health, less anxiety, and adequate dental treatment sought promptly [13]. Psychiatrists must consider the patient’s oral health when prescribing antipsychotics. Up-to-date guidelines must be available to all physicians concerning the appropriate use of these medications. It is critical to find the lowest possible dosage to maintain the patient’s fine motor function needed to brush and floss correctly, but most importantly, to reduce the overall adverse effects of these medications [15]. The prioritization of severe mental health symptoms over potential oral health issues may result in the under-recognition and undertreatment of dental diseases, such as xerostomia or oral cancer, in individuals with schizophrenia [35]. Because of this, dentists are encouraged to maintain an open communication channel and discussion with the physicians to inform the association of polypharmacy with xerostomia and dental diseases and the need to manage these conditions in a multi-disciplinary way [36].
5. Future Directions
Future progressive research is required to address the burden of oral illnesses and lessen the disparities that affect people with mental problems. E Joury, in their recent study, mentioned three examples of future research to improve oral health among people with mental disorders [18]. Regarding public health interventions, the research could evaluate the impact of water fluoridation or fluoride varnish on reducing oral health inequalities among schizophrenic patients. As far as health service interventions are concerned, designing financial models with incentives to include oral health as a part of mental health services would help deliver evidence-based oral health prevention and stabilization amongst these patients. Finally, social care interventions might include training caregivers on supporting oral healthcare routinely to these patients. An interdisciplinary team should conduct these in real-world settings, including all interventions [37]. Although these studies try to direct future research among people with any mental disorder, the same approach would be helpful for elderly schizophrenic patients.
6. Conclusions
Schizophrenia is a chronic heterogeneous psychological disorder that affects older adults. This study aimed to investigate the relationship between schizophrenia and dental health in the elderly population. The findings of our literature search underscore the need for targeted dental interventions to address the dental health challenges this vulnerable population faces. They highlight the importance of integrating dental health into the overall medical management of elderly individuals with schizophrenia. In terms of addressing the burden of oral diseases in elderly patients with schizophrenia, current dental research has been unable to develop efficient specific therapies. However, there is an emphasis on prioritizing preventive dentistry to minimize the occurrence and progression of dental conditions in this population.
Funding
The authors received no financial support for the research, authorship, and/or publication of this article.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Zhang, T.; Fang, Y.; Wang, L.; Gu, L.; Tang, J. Exosome and exosomal contents in schizophrenia. J. Psychiatr. Res. 2023, 163, 365–371. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization. International Classification of Diseases for Mortality and Morbidity Statistics, 11th ed.; WHO: Geneva, Switzerland, 2018. [Google Scholar]
- Mueser, K.T.; McGurk, S.R. Schizophrenia. Lancet 2004, 363, 2063–2072. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kilbourne, A.M.; Horvitz-Lennon, M.; Post, E.P.; McCarthy, J.F.; Cruz, M.; Welsh, D.; Blow, F.C. Oral health in Veterans Affairs patients diagnosed with serious mental illness. J. Public Health Dent. 2007, 67, 42–48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kiyak, H.A.; Reichmuth, M. Barriers to and Enablers of Older Adults’ Use of Dental Services. J. Dent. Educ. 2005, 69, 975–986. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gupta, S.; Pk, P.; Gupta, R. Necessity of oral health intervention in schizophrenic patients—A review. Nepal J. Epidemiol. 2016, 6, 605–612. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dickerson, F.B.; McNary, S.W.; Brown, C.H.; Kreyenbuhl, J.; Goldberg, R.W.; Dixon, L.B. Somatic Healthcare Utilization Among Adults With Serious Mental Illness Who Are Receiving Community Psychiatric Services. Med. Care 2003, 41, 560–570. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Janardhanan, T.; Cohen, C.I.; Kim, S.; Rizvi, B.F. Dental Care and Associated Factors Among Older Adults With Schizophrenia. J. Am. Dent. Assoc. 2011, 142, 57–65. [Google Scholar] [CrossRef] [Scilit]
- Kurokawa, Y.; Watanabe, S.; Miyabe, S.; Ishibashi, K.; Yamamoto, S.; Goto, M.; Hasegawa, S.; Miyachi, H.; Fujita, K.; Nagao, T. Oral hygiene status and factors related to oral health in hospitalized patients with schizophrenia. Int. J. Dent. Hyg. 2022, 20, 658–663. [Google Scholar] [CrossRef] [Scilit]
- Ngo, D.Y.J.; Thomson, W.M.; Subramaniam, M.; Abdin, E.; Ang, K.-Y. The oral health of long-term psychiatric inpatients in Singapore. Psychiatry Res. 2018, 266, 206–211. [Google Scholar] [CrossRef] [Scilit]
- Zusman, S.P.; Ponizovsky, A.M.; Dekel, D.; Masarwa, A.-E.; Ramon, T.; Natapov, L.; Grinshpoon, A. An assessment of the dental health of chronic institutionalized patients with psychiatric disease in Israel. Spéc. Care Dent. 2010, 30, 18–22. [Google Scholar] [CrossRef] [Scilit]
- Denis, F.; Siu-Paredes, F.; Maitre, Y.; Amador, G.; Rude, N. A qualitative study on experiences of persons with schizophrenia in oral-health-related quality of life. Braz. Oral Res. 2021, 35, e050. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grinshpoon, A.; Zusman, S.P.; Weizman, A.; Ponizovsky, A.M. Dental Health and the Type of Antipsychotic Treatment in Inpatients with Schizophrenia. Isr. J. Psychiatry Relat. Sci. 2015, 52, 114–118. [Google Scholar] [PubMed]
- Wey, M.C.; Loh, S.; Doss, J.G.; Abu Bakar, A.K.; Kisely, S. The oral health of people with chronic schizophrenia: A neglected public health burden. Aust. N. Z. J. Psychiatry 2016, 50, 685–694. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tani, H.; Uchida, H.; Suzuki, T.; Shibuya, Y.; Shimanuki, H.; Watanabe, K.; Den, R.; Nishimoto, M.; Hirano, J.; Takeuchi, H.; et al. Dental conditions in inpatients with schizophrenia: A large-scale multi-site survey. BMC Oral Health 2012, 12, 32. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chu, K.-Y.; Yang, N.-P.; Chou, P.; Chiu, H.-J.; Chi, L.-Y. Factors associated with dental caries among institutionalized residents with schizophrenia in Taiwan: A cross-sectional study. BMC Public Health 2010, 10, 482. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chu, K.-Y.; Yang, N.-P.; Chou, P.; Chi, L.-Y.; Chiu, H.-J. The Relationship between Body Mass Index, the Use of Second-Generation Antipsychotics, and Dental Caries among Hospitalized Patients with Schizophrenia. Int. J. Psychiatry Med. 2011, 41, 343–353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joury, E.; Kisely, S.; Watt, R.; Ahmed, N.; Morris, A.; Fortune, F.; Bhui, K. Mental Disorders and Oral Diseases: Future Research Directions. J. Dent. Res. 2023, 102, 5–12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choi, J.; Price, J.; Ryder, S.; Siskind, D.; Solmi, M.; Kisely, S. Prevalence of dental disorders among people with mental illness: An umbrella review. Aust. New Zealand J. Psychiatry 2022, 56, 949–963. [Google Scholar] [CrossRef] [Scilit]
- Albahli, B.F.; Alrasheed, N.M.; Alabdulrazaq, R.S.; Alasmari, D.S.; Ahmed, M.M. Association between schizophrenia and periodontal disease in relation to cortisol levels: An ELISA-based descriptive analysis. Egypt. J. Neurol. Psychiatry Neurosurg. 2021, 57, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Meyer, U.; Schwarz, M.J.; Müller, N. Inflammatory processes in schizophrenia: A promising neuroimmunological target for the treatment of negative/cognitive symptoms and beyond. Pharmacol. Ther. 2011, 132, 96–110. [Google Scholar] [CrossRef] [Scilit]
- Saetre, P.; Emilsson, L.; Axelsson, E.; Kreuger, J.; Lindholm, E.; Jazin, E. Inflammation-related genes up-regulated in schizophrenia brains. BMC Psychiatry 2007, 7, 46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stein, D.J.; Benjet, C.; Gureje, O.; Lund, C.; Scott, K.M.; Poznyak, V.; van Ommeren, M. Integrating mental health with other non-communicable diseases. BMJ 2019, 364, l295. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Senusi, A.; Higgins, S.; Fortune, F. The influence of oral health and psycho-social well-being on clinical outcomes in Behçet’s disease. Rheumatol. Int. 2018, 38, 1873–1883. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gomaa, N.; Tenenbaum, H.; Glogauer, M.; Quiñonez, C. The Biology of Social Adversity Applied to Oral Health. J. Dent. Res. 2019, 98, 1442–1449. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hashioka, S.; Inoue, K.; Miyaoka, T.; Hayashida, M.; Wake, R.; Oh-Nishi, A.; Inagaki, M. The Possible Causal Link of Periodontitis to Neuropsychiatric Disorders: More Than Psychosocial Mechanisms. Int. J. Mol. Sci. 2019, 20, 3723. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Matevosyan, N.R. Oral Health of Adults with Serious Mental Illnesses: A Review. Community Ment. Health J. 2009, 46, 553–562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Velasco-Ortega, E.; Segura-Egea, J.; Cordoba-Arenas, S.; Jimenez-Guerra, A.; Monsalve-Guil, L.; Lopez-Lopez, J. A comparison of the dental status and treatment needs of older adults with and without chronic mental illness in Sevilla, Spain. Med. Oral Patol. Oral Cirugía Bucal 2013, 18, e71–e75. [Google Scholar] [CrossRef] [Scilit]
- Keepers, G.A.; Fochtmann, L.J.; Anzia, J.M.; Benjamin, S.; Lyness, J.M.; Mojtabai, R.; Servis, M.; Walaszek, A.; Buckley, P.; Lenzenweger, M.F.; et al. The American Psychiatric Association Practice Guideline for the Treatment of Patients with Schizophrenia. Am. J. Psychiatry 2020, 33, 63–66. [Google Scholar]
- Stroup, T.S.; Gray, N. Management of common adverse effects of antipsychotic medications. World Psychiatry 2018, 17, 341–356. [Google Scholar] [CrossRef] [Scilit]
- Winterer, G. Why do patients with schizophrenia smoke? Curr. Opin. Psychiatry 2010, 23, 112–119. [Google Scholar] [CrossRef] [Scilit]
- Yadav, S.; Yang, Y.; Dutra, E.H.; Robinson, J.L.; Wadhwa, S. Temporomandibular Joint Disorders in Older Adults. J. Am. Geriatr. Soc. 2018, 66, 1213–1217. [Google Scholar] [CrossRef] [Scilit]
- Gurbuz, O.; Alatas, G.; Kurt, E. Prevalence of temporomandibular disorder signs in patients with schizophrenia. J. Oral Rehabil. 2009, 36, 864–871. [Google Scholar] [CrossRef] [Scilit]
- Sadowsky, J.M.; Thomas, E.; Simmons, R.K.; Edwards, L.P.; Johnson, C.D. 4 case reports: Dental management of patients with drug induced Tardive Dyskinesia (TD). J. Dent. Health Oral Disord. Ther. 2014, 1, 18–21. [Google Scholar]
- Swager, L.; Morgan, S. Psychotropic-induced dry mouth: Don’t overlook this potentially serious side effect. Curr. Psychiatry 2011, 10, 54–58. [Google Scholar]
- Okamoto, A.; Miyachi, H.; Tanaka, K.; Chikazu, D.; Miyaoka, H. Relationship between xerostomia and psychotropic drugs in patients with schizophrenia: Evaluation using an oral moisture meter. J. Clin. Pharm. Ther. 2016, 41, 684–688. [Google Scholar] [CrossRef] [Scilit]
- McNeil, D.; Randall, C.; Baker, S.; Borrelli, B.; Burgette, J.; Gibson, B.; Heaton, L.; Kitsaras, G.; McGrath, C.; Newton, J. Consensus Statement on Future Directions for the Behavioral and Social Sciences in Oral Health. J. Dent. Res. 2022, 101, 619–622. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).