1. Introduction
Digital dentistry has revolutionized clinical workflows by enabling precise 3D modeling of the oral cavity for diagnostics, prosthetics, and orthodontic treatment planning [
1]. Intraoral scanners (IOS) have become the gold standard in this domain, offering high accuracy and real-time visualization capabilities [
2]. However, despite their clinical benefits, the widespread adoption of high-performance IOS systems is often hindered by their high acquisition costs, complex maintenance requirements, and steep learning curves, particularly in primary care settings or developing regions [
3]. Consequently, there is a growing interest in leveraging cost-effective RGB intraoral cameras (IOC) as accessible alternatives for dental documentation and telemedicine [
4].
While RGB intraoral cameras are affordable and user-friendly, they suffer from a significant technical limitation: a narrow Field of View (FOV) [
5]. A single image captures only a few teeth, necessitating the application of image stitching techniques to generate a comprehensive panoramic view of the dental arch [
6]. However, the oral cavity presents a uniquely challenging environment for traditional computer vision algorithms. First, the tooth surface (enamel) is inherently textureless and features repetitive patterns, which often causes the failure of hand-crafted feature detectors such as Scale-Invariant Feature Transform (SIFT) or Oriented FAST and Rotated BRIEF (ORB) due to a lack of distinct keypoints [
7]. Second, the oral environment is wet, leading to severe specular highlights caused by saliva and illumination sources. These reflections shift with camera movement, creating false features (outliers) that degrade the accuracy of image registration [
8]. Recent studies on low-texture scene stitching have consistently highlighted the inadequacy of traditional methods in such adverse conditions [
9]. In particular, sequential alignment along a curved mandibular arch often induces cumulative curvature distortion (the so-called banana effect), which degrades the geometric stability of 2D stitched panoramas.
The advent of deep learning has provided new avenues for overcoming these matching challenges. Learned local features, such as those extracted by Convolutional Neural Networks (CNNs), have demonstrated improved robustness against illumination changes and textureless regions compared to traditional descriptors [
10]. In particular, the combination of SuperPoint [
11] for self-supervised interest point detection and SuperGlue [
12] for graph-based feature matching has set new benchmarks in geometric computer vision. Recent applications of these models in challenging environments, such as low-light remote sensing [
13] and repetitive structural defect detection [
14], suggest their potential applicability to the texture-poor and repetitive nature of dental imagery.
Indeed, recent advancements have further substantiated this potential in the dental domain. A systematic review [
15] analyzed deep learning methodologies in dental image analysis, while other studies [
16] demonstrated the automated processing of intraoral clinical photographs. Furthermore, deep learning techniques have been applied to point cloud patching in intraoral scanning to address data incompleteness [
17]. In the context of geometric matching, the robustness of SuperPoint and SuperGlue has been validated in stereo vision SLAM [
18], reinforcing the suitability of these descriptors for challenging estimation tasks.
However, robust algorithms alone cannot guarantee successful clinical implementation. The quality of handheld scanning is heavily influenced by acquisition parameters such as working distance and overlap ratio. While extensive studies have optimized scanning protocols for 3D IOS devices—identifying specific distance ranges (e.g., 5–10 mm) to minimize trueness errors [
19,
20]—similar guidelines for 2D handheld panoramic stitching are notably absent. Capturing images at an improper distance or with insufficient overlap can lead to geometric distortions, drift errors, and ultimately, stitching failure.
To address these gaps, this study proposes a robust stitching framework for RGB intraoral cameras and identifies the optimal acquisition parameters for handheld operation. We introduce a deep learning-based pipeline utilizing SuperPoint and SuperGlue to ensure robust feature matching in the presence of specular highlights and textureless surfaces. Furthermore, we experimentally investigate the impact of working distance (1.5 cm to 3.0 cm) and overlap ratio on stitching success rates and geometric integrity. This work aims to validate the feasibility of generating reliable 2D dental panoramas using consumer-grade sensors and to establish a standardized acquisition protocol for their clinical application. This study focuses exclusively on the mandibular arch using a physical dental phantom to provide a controlled and repeatable evaluation setting. The main contributions are as follows: (1) a deep feature matching-based stitching framework combined with a central-reference strategy to suppress cumulative curvature distortion, (2) experimental optimization of acquisition parameters (working distance and overlap) for low-cost handheld RGB intraoral cameras, and (3) quantitative geometric validation using repeated physical measurements of mandibular arch dimensions as ground-truth references.
2. Materials and Methods
2.1. System Configuration and Dataset Acquisition
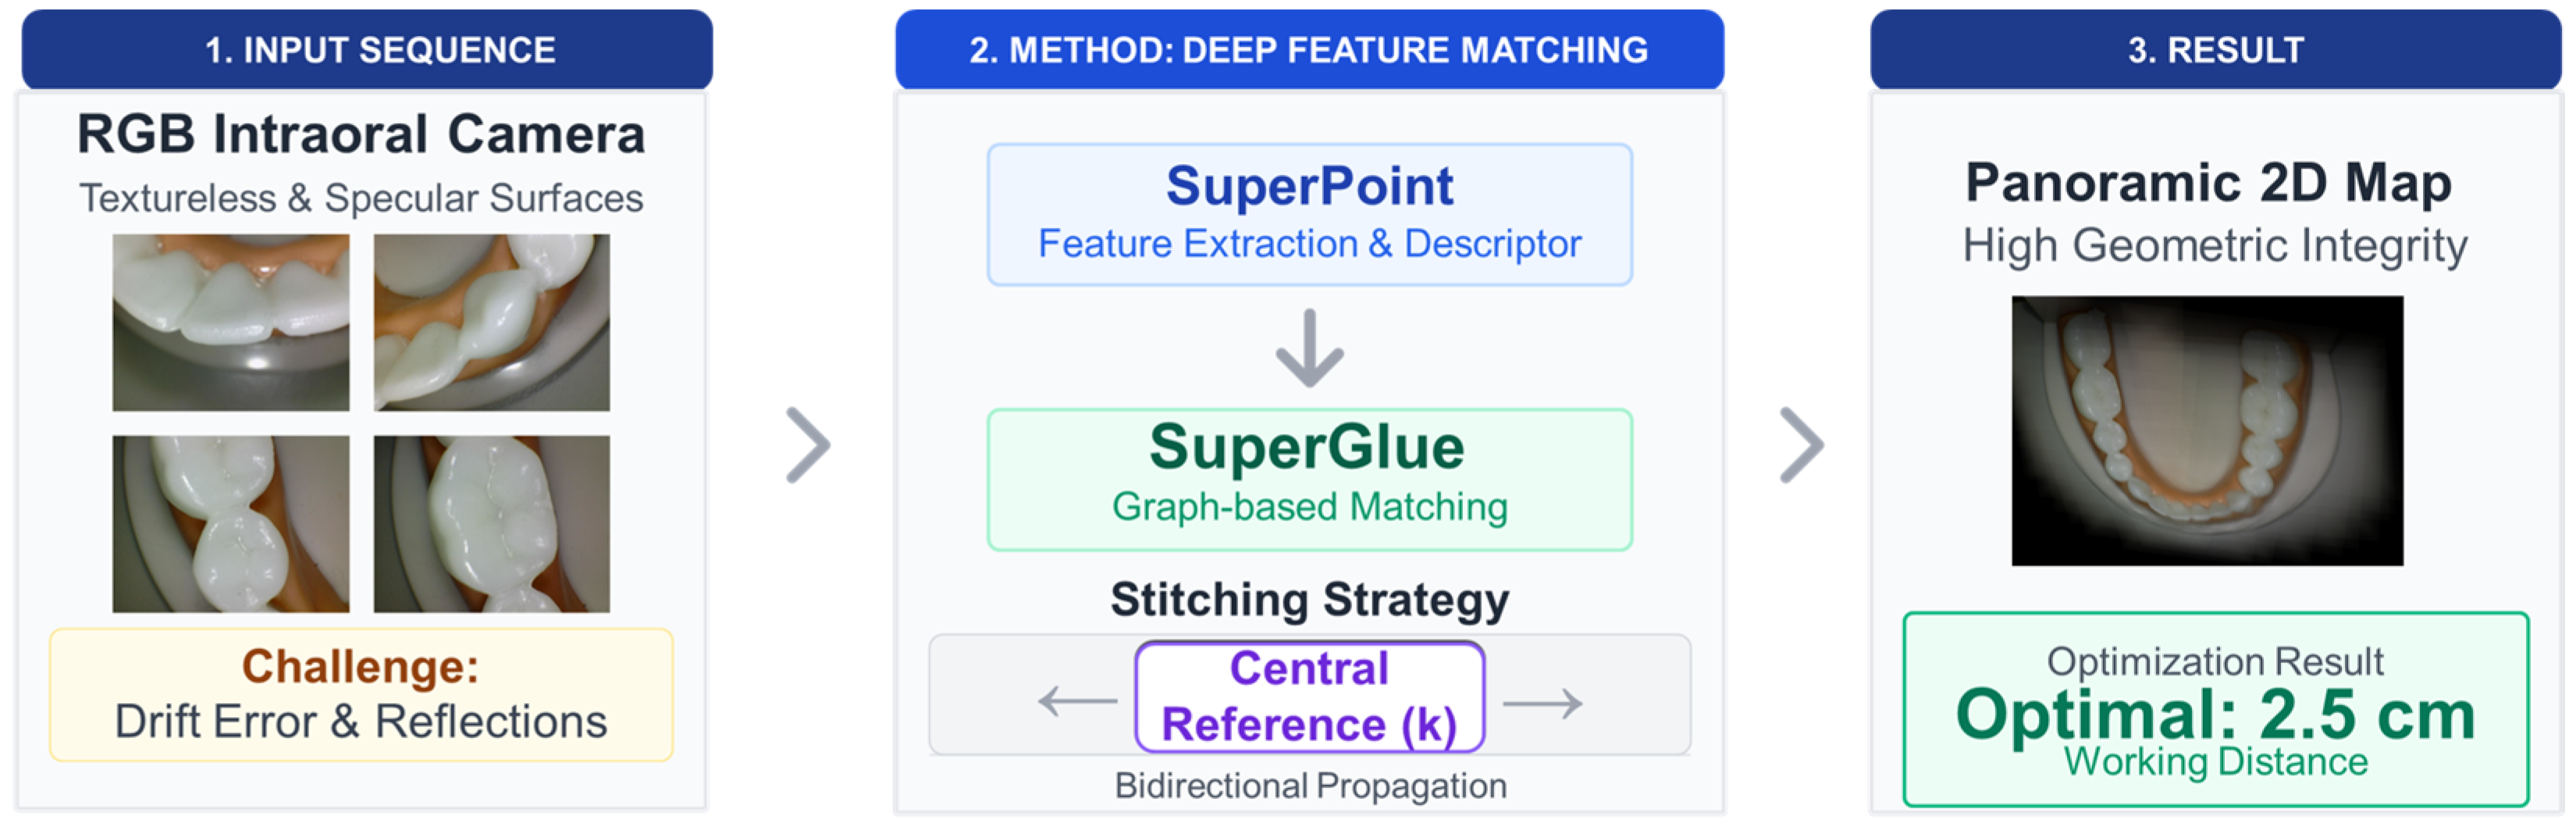
The overall framework of the proposed intraoral image stitching system, including the deep feature matching pipeline and the acquisition parameter optimization strategy, is illustrated in
Figure 1.
The imaging system utilized in this study consists of a commercial handheld RGB intraoral camera (EzCam; Vatech, Hwaseong, Republic of Korea) equipped with a CMOS sensor, delivering video sequences at a resolution of 1920 1080 pixels. To simulate clinical environments while controlling variables, a standard dental typodont (phantom) model Dental Model; Dubiduba, Beijing, China was used.
The dataset
consists of sequential frames captured by moving the camera along the dental arch:
where
represents the total number of frames in a single scanning sequence acquired under fixed acquisition parameters. The acquisition protocol was strictly controlled by varying the working distance (
cm) and the frame overlap ratio (
) to quantitatively analyze the impact of acquisition geometry on stitching performance. All sequences were acquired exclusively from the mandibular phantom. For the working-distance study, three independent scan sequences (v1–v3) were acquired at each distance (1.5, 2.0, 2.5, and 3.0 cm), and the frame counts per sequence are reported in the
Appendix A (
Table A1). For the overlap-ratio study, additional single scan sequences were acquired under approximately 1/3 and 1/2 overlap conditions at each distance; these sequences constitute the experimental trials used to compute the SSR in
Section 2.6, and their frame counts are summarized in the experimental results section.
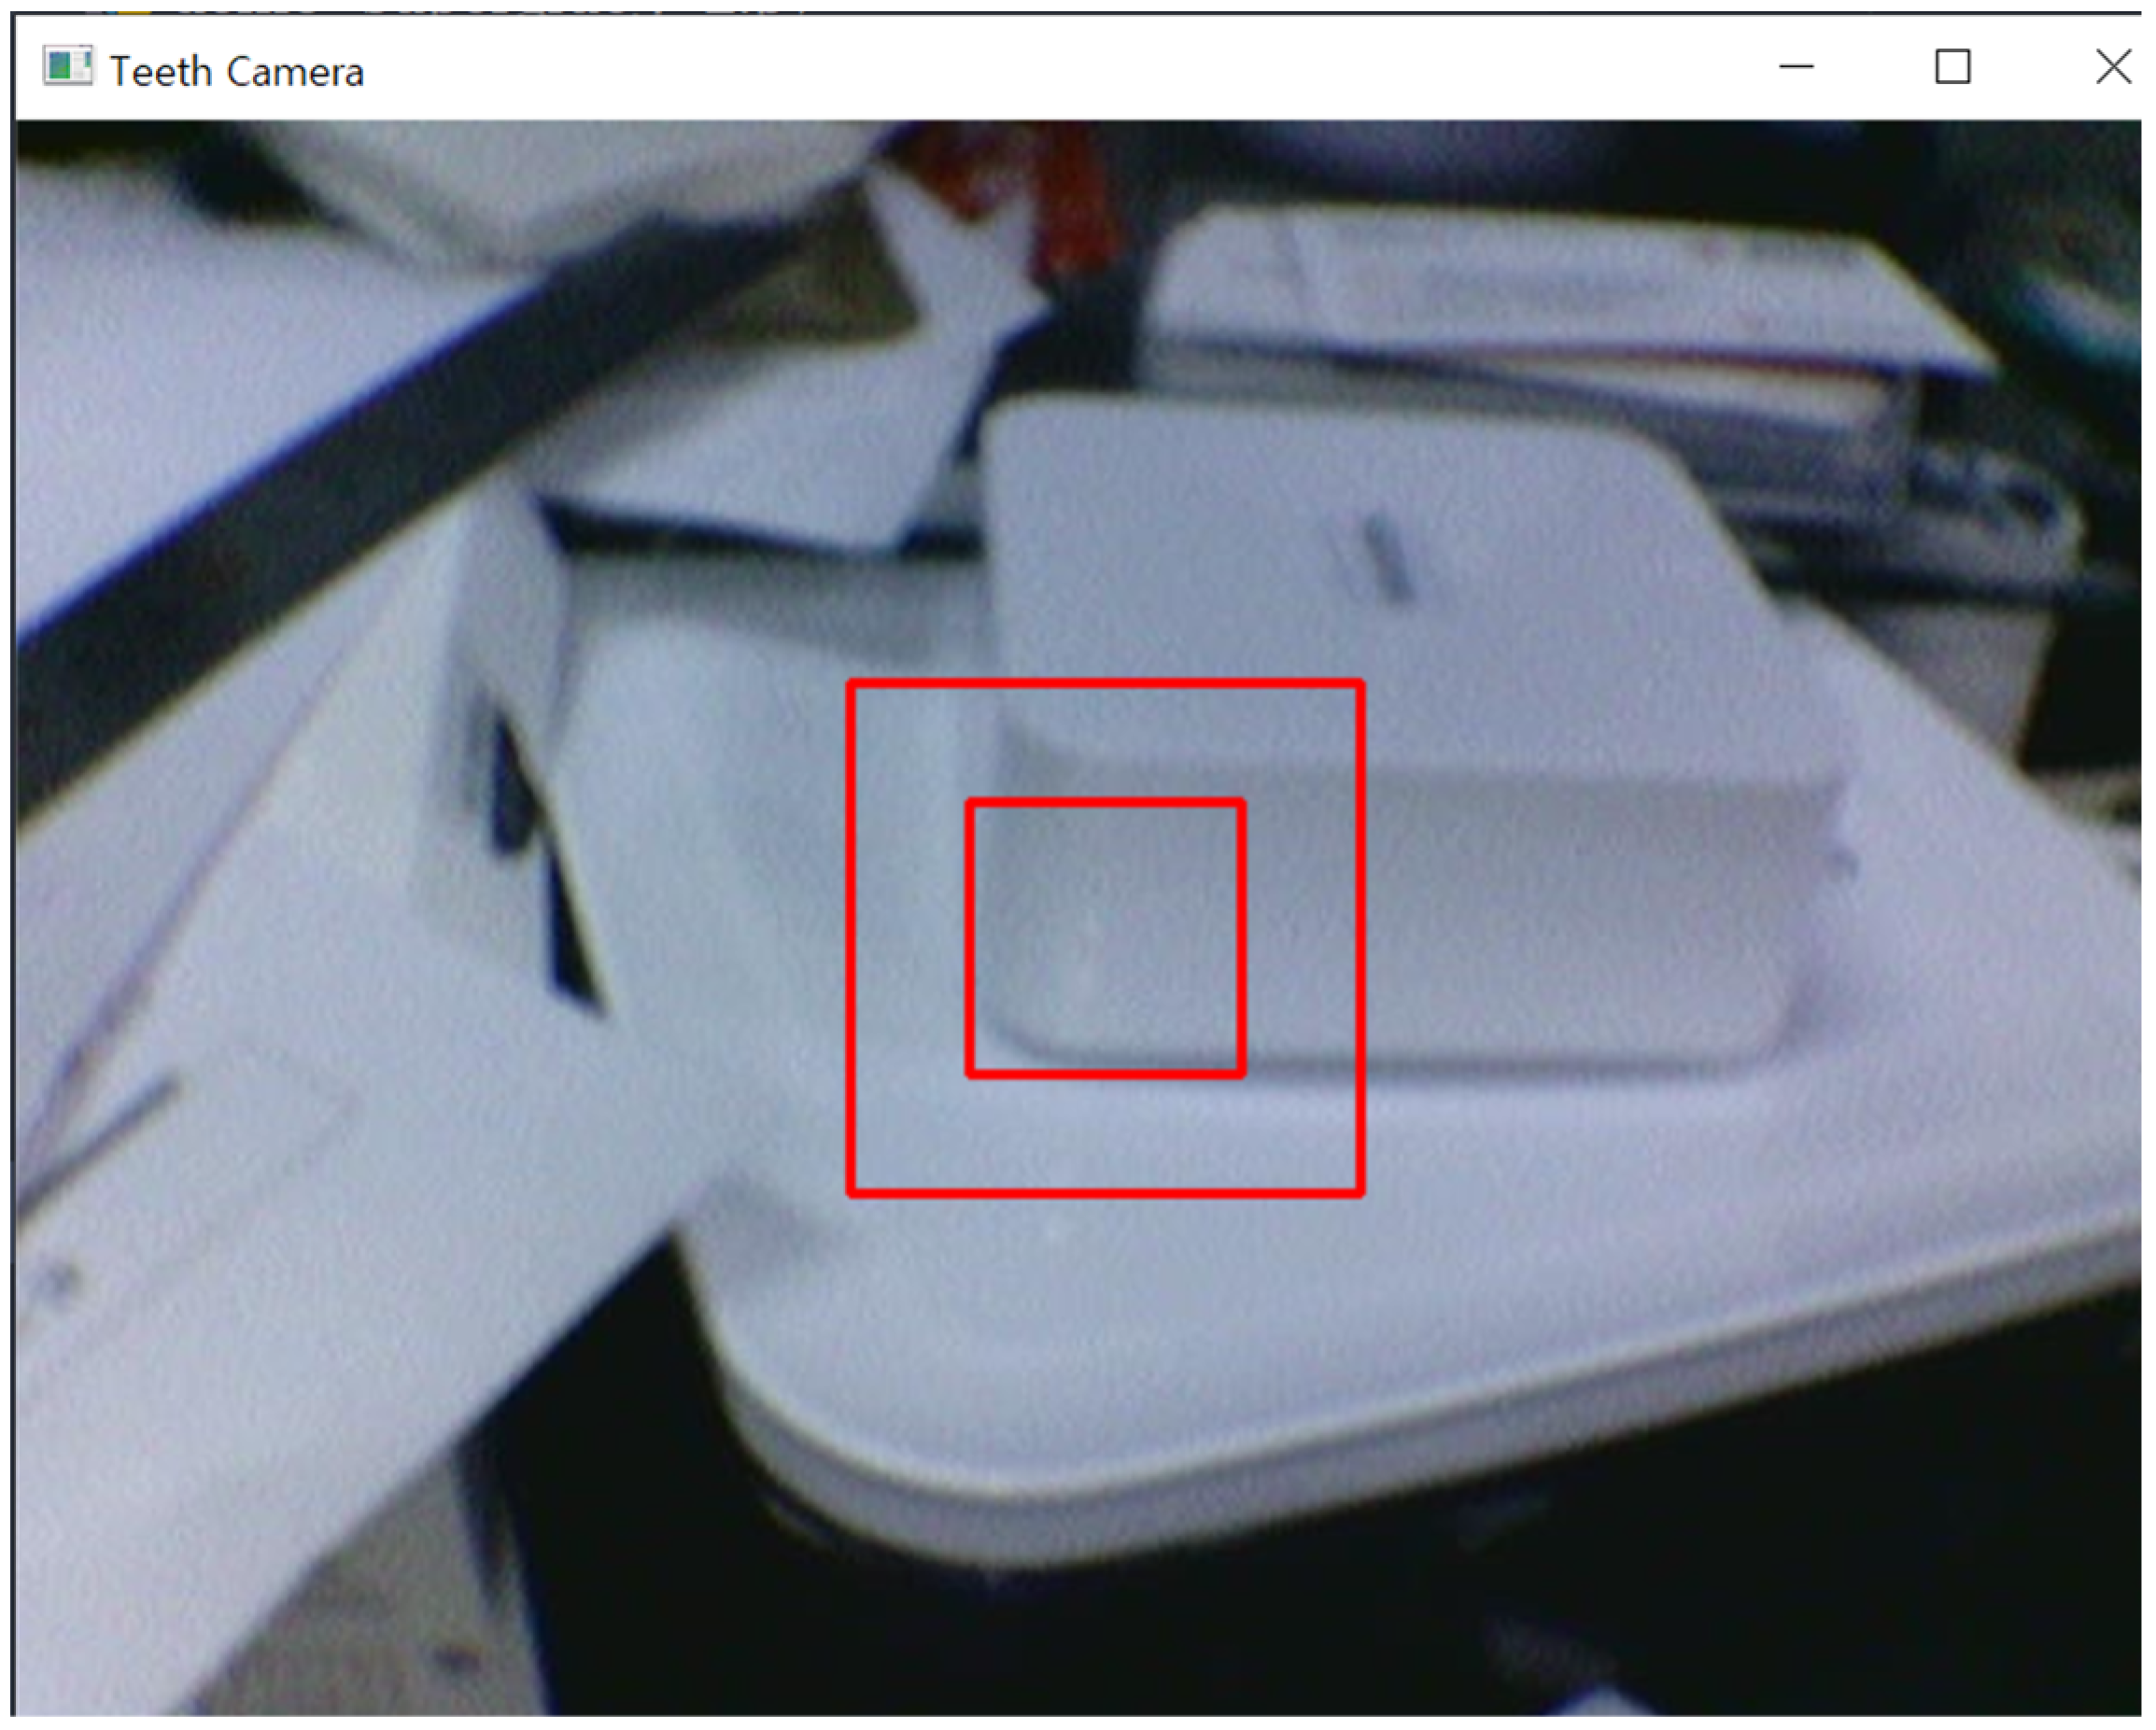
To ensure consistent data acquisition and minimize operator variability, a custom-developed software interface was utilized. As shown in the experimental setup (
Figure 2), the software provides real-time visual guides (bounding boxes) on the live feed, consisting of a larger box for molars and a smaller box for anterior teeth. These guides assist the operator in maintaining a constant working distance and appropriate framing during the handheld scan, simulating a guided clinical workflow.
2.2. Pre-Processing: Contrast Limited Adaptive Histogram Equalization (CLAHE)
Intraoral images frequently suffer from uneven illumination and specular highlights caused by the wet surface of teeth. To enhance local contrast and suppress noise amplification in homogeneous regions (textureless enamel), we applied Contrast Limited Adaptive Histogram Equalization (CLAHE).
The image is divided into non-overlapping tiles of size
. For each tile, the histogram is computed and clipped at a predefined limit
to prevent over-amplification of noise. The redistribution of clipped pixels is governed by:
where
is the histogram count for intensity level
, and
is the number of gray levels. Bilinear interpolation is then performed to eliminate artifacts at tile boundaries, yielding the pre-processed frame
.
2.3. Deep Feature Extraction and Matching
Conventional handcrafted descriptors (e.g., SIFT, ORB) fail to extract sufficient keypoints in textureless dental surfaces. We employed a deep learning-based pipeline comprising SuperPoint for detection and SuperGlue for matching. We used publicly available pre-trained weights for SuperPoint and SuperGlue. No dental-domain fine-tuning was performed in this study, in order to evaluate out-of-the-box robustness under controlled phantom conditions.
2.3.1. SuperPoint Network
SuperPoint serves as a shared encoder–decoder architecture. The encoder maps the input image to a feature map. Two decoder heads then operate in parallel:
Interest Point Decoder: Computes a probability map for keypoint locations using a softmax activation. The loss function for keypoint detection is defined as a cross-entropy loss between the predicted logits and the pseudo-ground truth labels.
Descriptor Decoder: Outputs a dense descriptor map
. The descriptor loss
is a hinge loss that enforces matching descriptors to be close and non-matching ones to be far apart:
where
if keypoints
and
correspond, and 0 otherwise.
and
are the positive and negative margins, respectively.
2.3.2. SuperGlue Matching with Graph Neural Networks
To handle the large displacement and repetitive patterns of teeth, we utilized SuperGlue, an attentional Graph Neural Network (GNN). Given two sets of local features and from images and , SuperGlue constructs a complete graph where nodes are keypoints.
The matching process is formulated as an optimal transport problem. The assignment matrix
is computed to maximize the total score
, where
is the affinity score matrix derived from the GNN. The Sinkhorn algorithm is iteratively applied to enforce the doubly stochastic constraints:
This method allows for robust rejection of outliers (mismatched teeth) by assigning them to a “dustbin” node, demonstrating substantially improved robustness compared to nearest neighbor search in specular environments.
2.4. Stitching Strategy: Central-Reference Homography and TPS Deformation
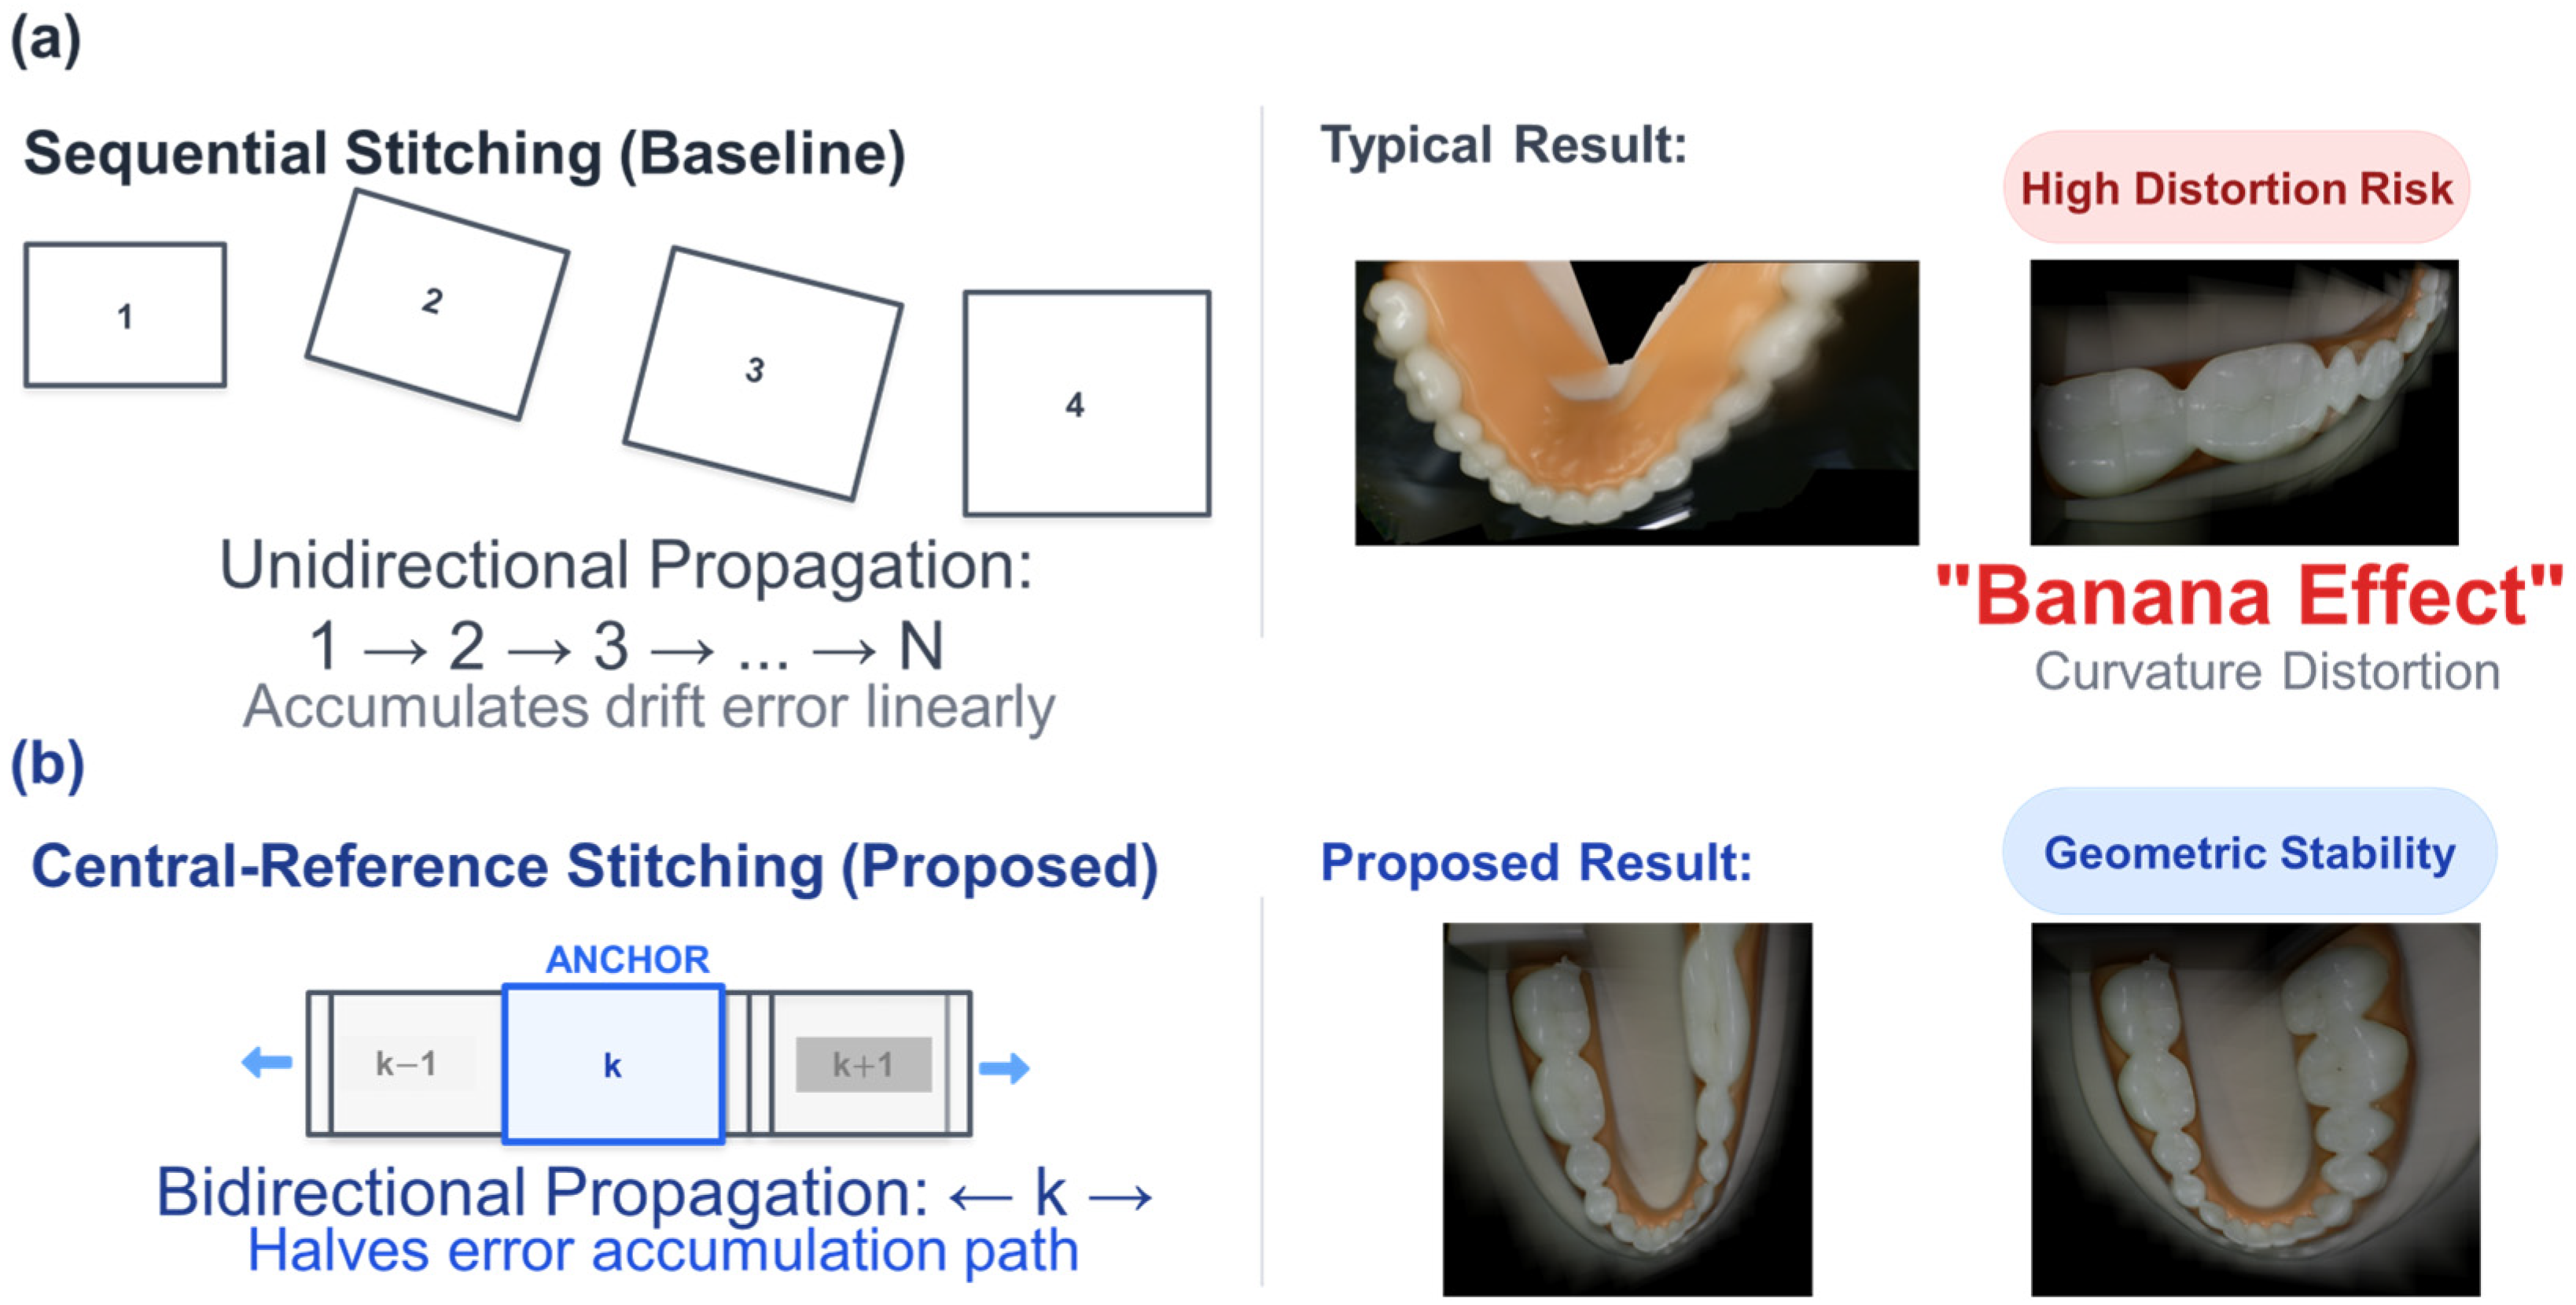
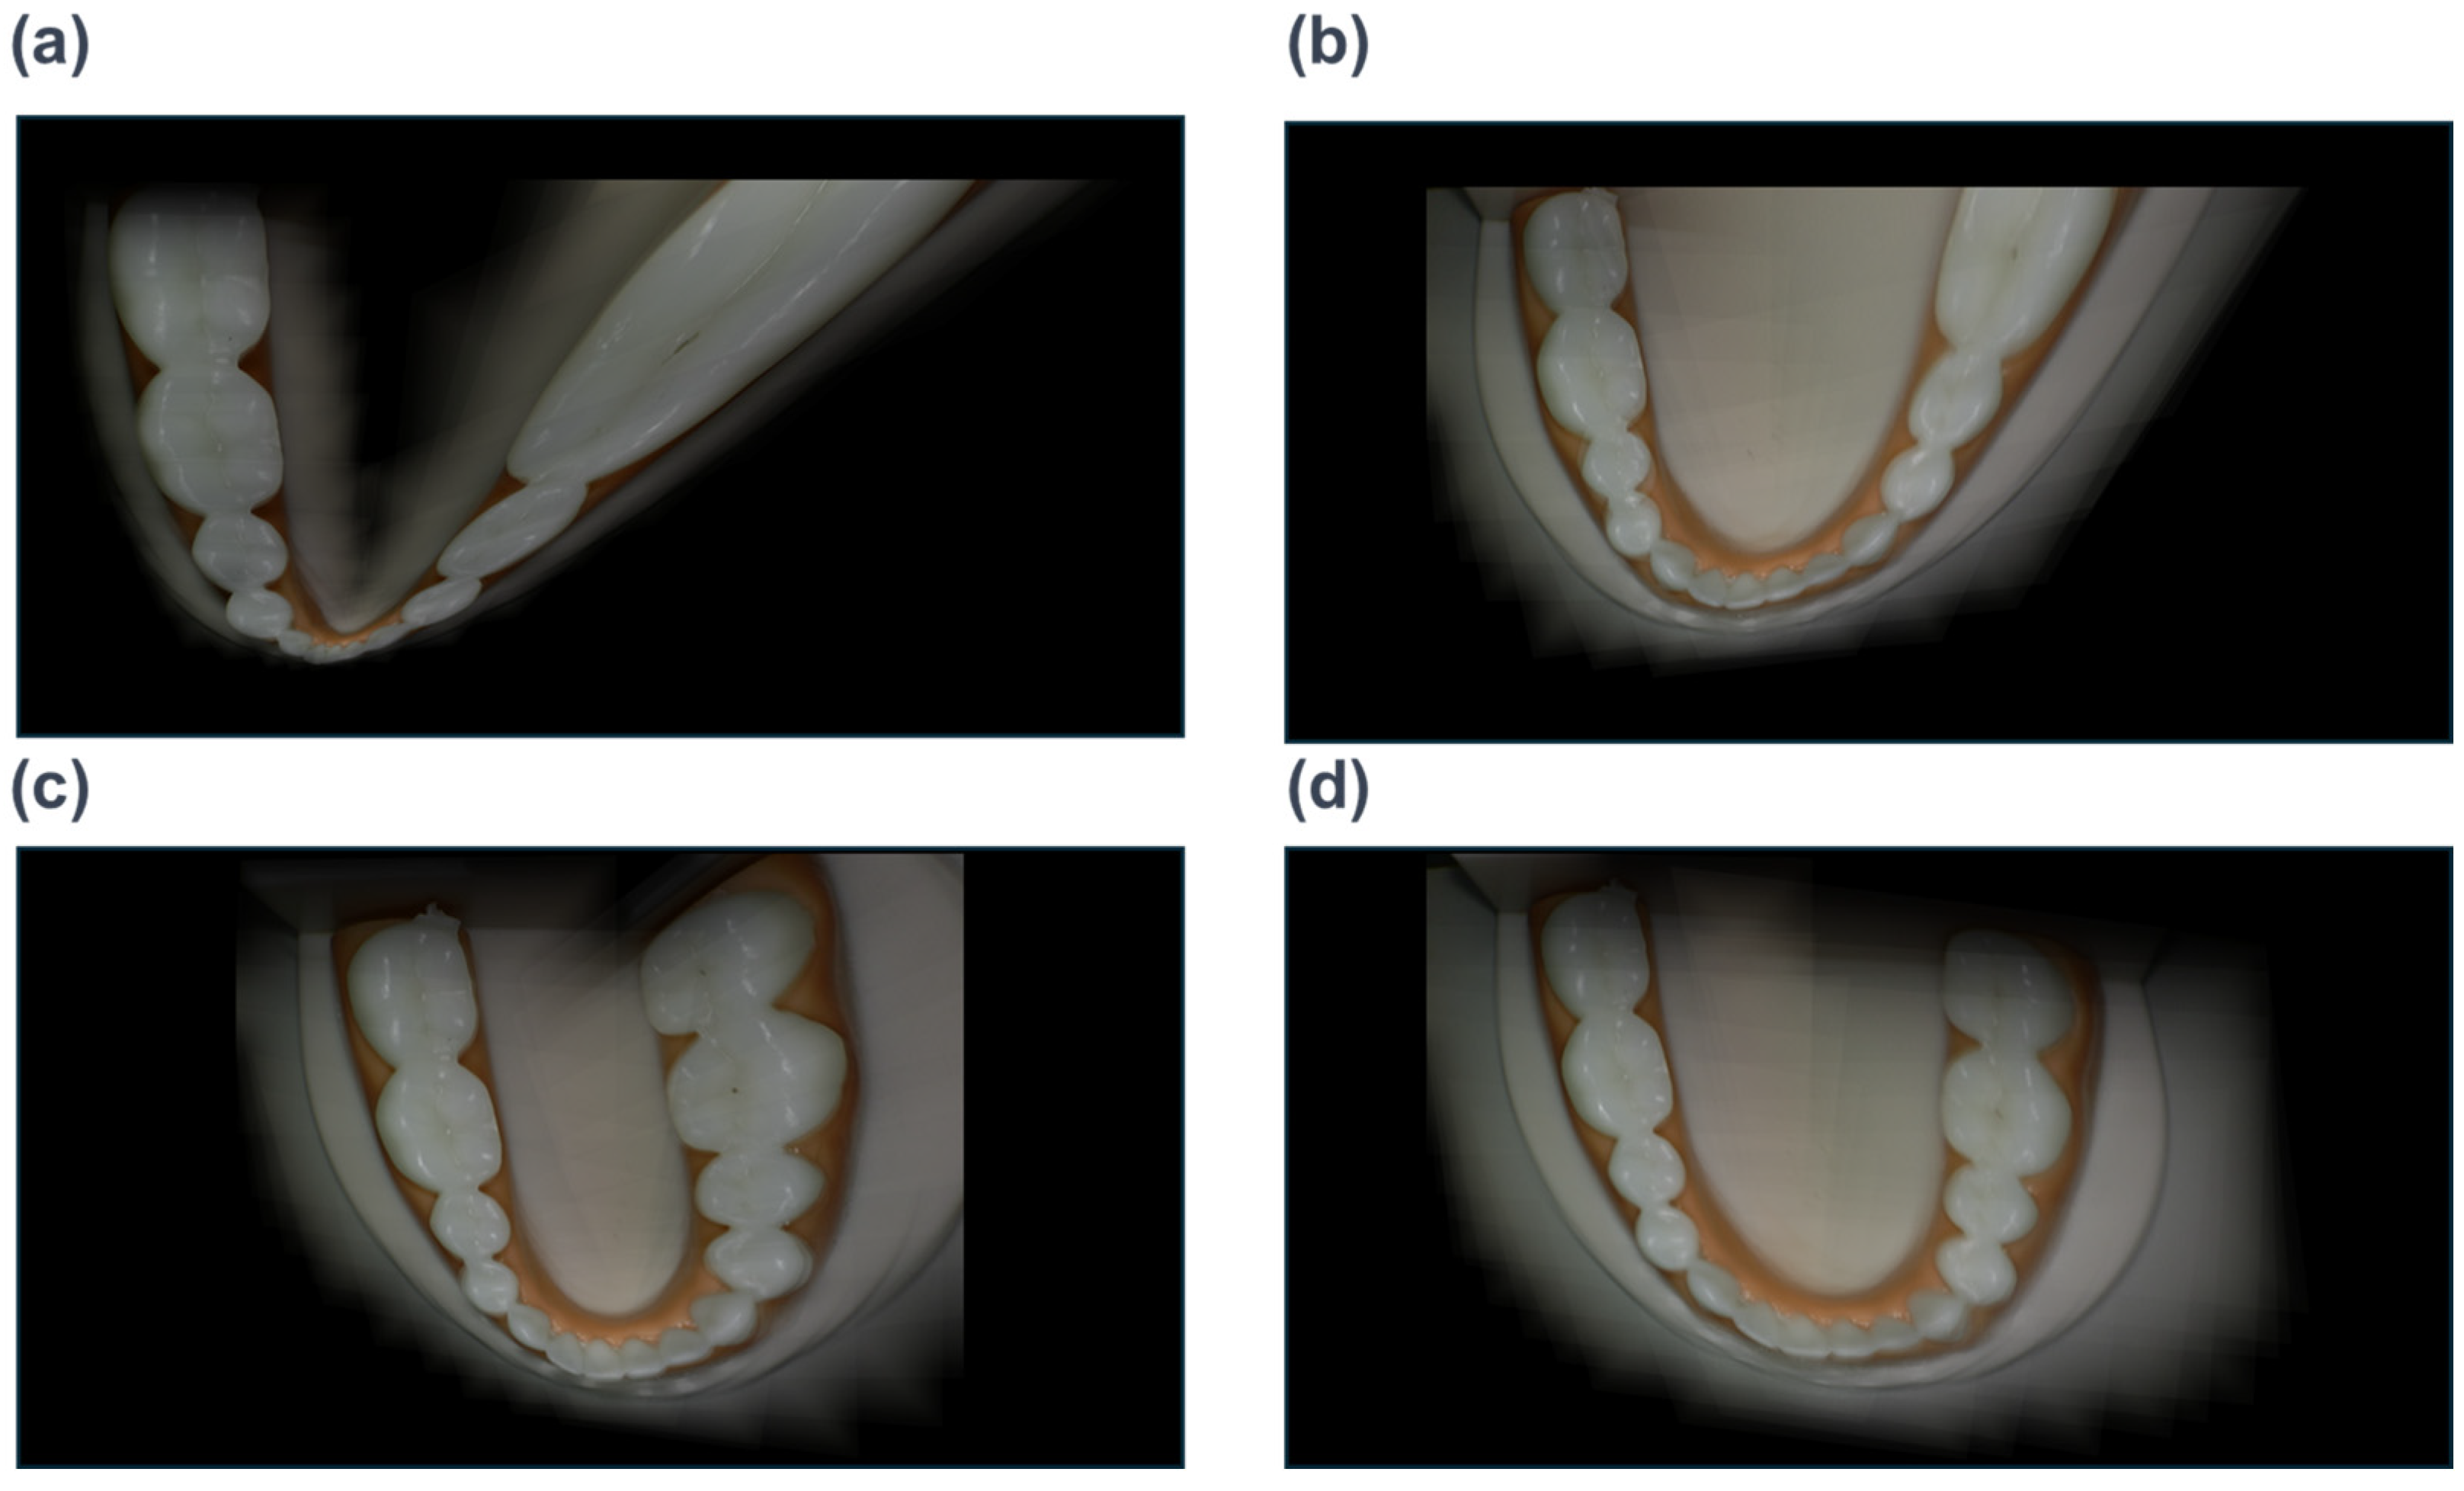
A major challenge in scanning the dental arch is the accumulation of drift error and local misalignments caused by the non-planar geometry of teeth. This recursive transformation typically results in the “banana effect” or severe distortion at the sequence end, as illustrated in
Figure 3a. To address this, we implemented a two-stage alignment strategy combining global Central-Reference Homography and local Thin-Plate Spline (TPS) Deformation. First, to mitigate the drift error, we employed a central-reference strategy (
Figure 3b). Instead of propagating transforms from the first frame, we select the central frame
as the anchor. The global homography
is computed bidirectionally, halving the error accumulation path:
However, homography is a rigid planar transformation that cannot perfectly align the curved 3D surfaces of teeth. To correct residual local misalignments, we applied Thin-Plate Spline (TPS) deformation. TPS creates a smooth interpolation surface that maps the matched keypoints of the source image exactly to the target coordinates while minimizing the “bending energy” of the transformation. The objective function
for the TPS mapping function
is defined as:
By minimizing this energy, the algorithm ensures that the image is warped naturally to align overlapping tooth structures without introducing sharp artifacts. This non-rigid deformation significantly improves the seamlessness of the final panorama.
2.5. Multi-Band Blending
Simple linear blending or seam cuts often result in visible artifacts due to exposure differences and moving specular highlights on the tooth surface. We adopted a Multi-band Blending approach.
The image is decomposed into a Laplacian pyramid. Let
be the
-th level of the Laplacian pyramid for image
, and
be the Gaussian pyramid for the weight mask
. The blended image
is reconstructed from the blended pyramid
:
where
iterates over the overlapping images. The final panoramic image is obtained by summing the upsampled levels of
. This technique effectively merges high-frequency details (features) while smoothing out low-frequency discrepancies (lighting variations).
2.6. Evaluation Metrics
To quantitatively evaluate the proposed framework and the impact of acquisition parameters, we defined the following metrics:
Number of Inliers (): The count of valid feature matches after RANSAC geometric verification. Higher indicates a robust registration.
Stitching Success Rate (SSR): The ratio of (i.e., no visible breaks or major misalignments according to predefined evaluation guidelines) to the total number of experimental trials.
Here, one experimental trial corresponds to one complete scan sequence acquired under a fixed working-distance and overlap configuration.
Visual Quality Score (VQS): A qualitative assessment of geometric integrity and clinical interpretability of stitched panoramas. Five non-dentistry evaluators (two imaging researchers and three faculty members) independently rated each stitched result using a predefined rubric with four criteria: (i) continuity of the mandibular arch, (ii) absence of visible seams or ghosting, (iii) absence of missing-tooth or duplicated-tooth artifacts, and (iv) preservation of local tooth geometry. Each panorama was categorized into High, Medium, or Low based on the number of criteria satisfied. Inter-observer agreement was quantified using overall percent agreement and Fleiss’ kappa, and the resulting values are reported to support reproducibility. As the evaluators were not dental specialists, a clinician-based user study will be conducted in future work to further validate clinical relevance.
Computational Performance (Runtime): We measured the end-to-end processing time per stitched panorama, defined as the total time from completing a scan sequence acquisition to generating the final blended panorama (including feature extraction/matching, warping, and multi-band blending). Measurements were performed on a workstation equipped with an NVIDIA GeForce RTX 4080 GPU (NVIDIA, Santa Clara, CA, USA).
4. Discussion
4.1. Geometric Limitations of 2D Manifold Projection
While the proposed deep learning-based framework successfully addressed the local matching challenges on textureless and specular dental surfaces, our results revealed an inherent geometric limitation common to 2D stitching approaches: the “Arch Straightening Effect.”
As observed in the final panoramic images, the naturally U-shaped dental arch tends to flatten into a linear strip. This phenomenon occurs because the dental arch is fundamentally a 3-dimensional manifold with high curvature. When a sequence of images capturing this 3D structure is projected onto a 2D plane using pairwise homography transformations without 3D depth information, the algorithm minimizes the reprojection error between adjacent frames locally. However, lacking a global 3D constraint, these local optimizations accumulate, causing the global curvature to unroll.
Mathematically, homography creates a projective transformation that preserves collinearity but not necessarily metric properties like angles or distances over long sequences. Consequently, the molar regions (distal ends of the arch) exhibit significant stretching distortion, appearing wider than their actual anatomical proportions. This suggests that while 2D stitching is highly effective for visualization and documentation (e.g., creating a “dental map”), it cannot fully replace 3D intraoral scanners for applications requiring high metric accuracy, such as prosthetic fabrication or orthodontic aligner planning. To overcome this, future studies must integrate Simultaneous Localization and Mapping (SLAM) or Neural Radiance Fields (NeRF) to recover the underlying 3D geometry.
4.2. Acquisition Parameter Optimization: The Trade-Off Between Stability and Resolution
Our experimental results highlight that the quality of handheld intraoral scanning is not solely dependent on the software algorithm but is critically governed by the acquisition parameters, specifically working distance and overlap ratio.
The identification of 2.5 cm as the optimal working distance can be explained by the trade-off between Feature Density and Spatial Resolution. At a distance of 1.5 cm, the Field of View (FOV) is extremely narrow, capturing less than one complete tooth per frame. This lack of distinct geometric context leads to the “aperture problem,” where the algorithm cannot distinguish the relative motion of the camera, resulting in a 0% success rate. Conversely, at 3.0 cm, while stability is maximized due to the inclusion of multiple teeth and gingival landmarks, the effective resolution (pixels per millimeter) drops significantly, potentially obscuring fine clinical details such as early enamel cracks or marginal discrepancies. Furthermore, a critical hardware limitation was observed regarding the autofocus mechanism. Commercial RGB cameras typically rely on contrast-based autofocus, which is prone to “focus hunting” behaviors, particularly at unstable working distances (e.g., 1.5 cm handheld) or during rapid movement. This instability creates a variable depth of field within a single sequence, causing intermittent blur that degrades the feature descriptor quality. Therefore, the superior stability observed at 2.5 cm is attributed not only to the optimal field of view but also to the maintenance of a consistent focal plane compared to the macro range. Regarding the overlap ratio, our finding that an approximately 1/3 overlap outperforms 1/2 overlap contradicts the common intuition in photogrammetry, which typically advocates higher overlap. In the context of pairwise homography-based stitching on texture-poor dental enamel, higher overlap does not necessarily improve correspondence quality because adjacent views can become overly redundant and ambiguous, especially under specular highlights and repetitive tooth patterns. As summarized in
Table 2, the recorded frame counts were not a monotonic function of overlap, indicating that practical handheld scanning dynamics also affect acquisition. Therefore, we attribute the superior stability at approximately 1/3 overlap to a more favorable balance between continuity and discriminative motion baseline for robust matching, rather than to frame count alone. Because the recorded frame counts were not a monotonic function of overlap in our handheld acquisition (
Table 2), we do not attribute the observed geometric differences to frame count alone. Instead, we interpret the superior stability at approximately 1/3 overlap as a more favorable balance between continuity and discriminative baseline for robust matching.
4.3. Clinical Feasibility and Practical Applications
The proposed system, using a standard RGB camera, demonstrates clear clinical utility as a cost-effective screening and documentation tool. Unlike traditional intraoral scanners that require significant investment and training, our approach utilizes equipment already available in many dental practices.
The generated panoramic images serve as excellent “Patient Communication Tools.” They allow clinicians to visualize the entire quadrant or arch in a single view, facilitating the explanation of hygiene status, multiple carious lesions, or gingival health to patients. Furthermore, this 2D mapping technology is particularly valuable for Tele-dentistry in remote areas, where transmitting a lightweight 2D panorama is far more bandwidth-efficient than sending large 3D mesh files.
However, clinicians must be aware of the metrological limitations. Due to the aforementioned straightening and stretching distortions, measurements taken directly from the stitched panorama (e.g., measuring the edentulous space for an implant) may not be accurate. Therefore, this technology should be positioned as a diagnostic aid rather than a measurement device.
4.4. Limitations and Future Directions
Despite the significant improvements in matching robustness, this study has limitations. First, the evaluation was primarily conducted on dental phantoms. All experiments were conducted on a mandibular phantom only; therefore, dynamic intraoral factors (tongue motion, saliva, patient movement) were not present in the evaluation setup. In future in vivo deployments, frame-quality filtering and motion-robust acquisition protocols will be incorporated to mitigate these effects. Although phantoms simulate the geometry of teeth, they lack the physiological micro-movements of the patient (e.g., tongue movement, breathing) and the variable saliva flow found in real clinical settings. Future in vivo studies are necessary to validate the robustness of the SuperPoint/SuperGlue pipeline against dynamic biological artifacts.
Second, the current processing time for deep feature matching is relatively high compared to real-time SIFT implementations. To enable live feedback for the clinician during scanning, model quantization or distillation techniques should be explored to accelerate the inference speed on edge devices.
Finally, the “straightening” artifact remains a critical hurdle. We propose that future research focuses on Hybrid Approaches that combine 2D deep stitching with lightweight depth estimation networks (Monocular Depth Estimation) to correct the manifold curvature, bridging the gap between 2D panoramas and true 3D reconstruction.
5. Conclusions
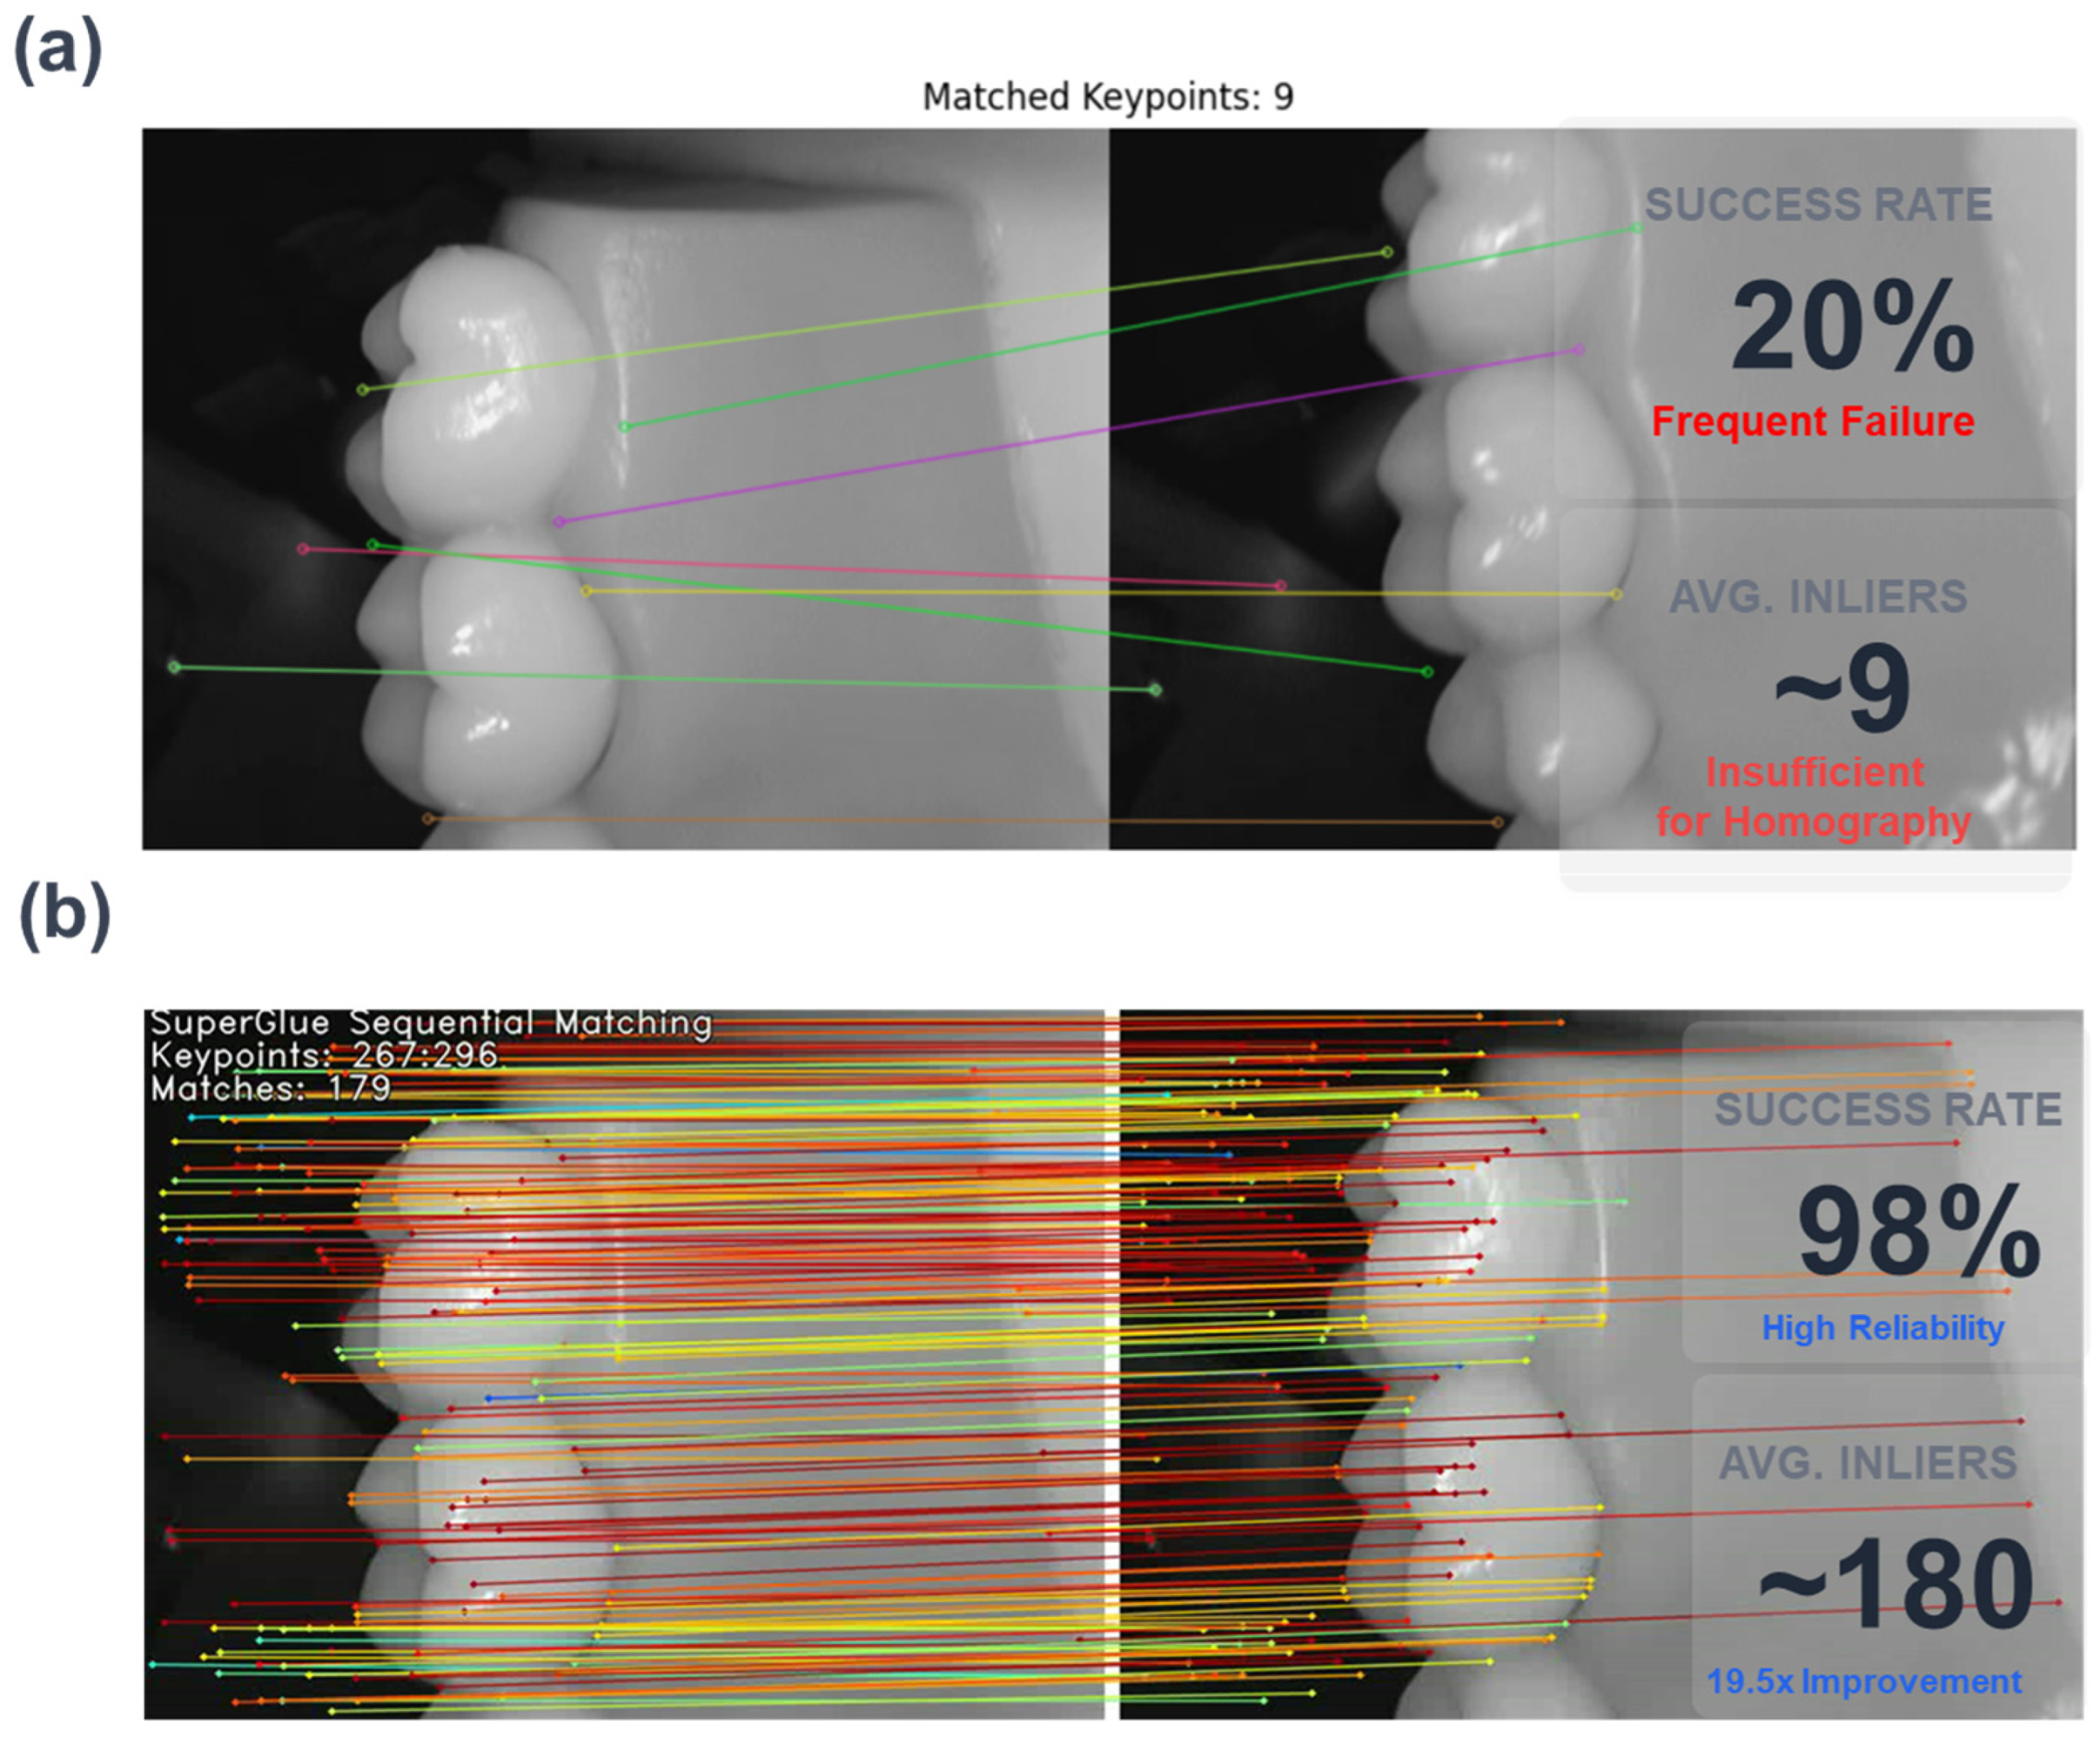
This study successfully demonstrated the feasibility of generating reliable 2D dental panoramas using consumer-grade RGB intraoral cameras, overcoming the inherent challenges of textureless enamel surfaces and severe specular highlights. By integrating a deep learning-based pipeline utilizing SuperPoint and SuperGlue, we achieved robust feature matching with approximately 20 times more valid inliers compared to traditional SIFT-based methods, thereby enhancing registration stability in handheld scanning scenarios.
Furthermore, our systematic experiments on acquisition parameters revealed that the quality of panoramic stitching is highly sensitive to the geometric conditions of data capture. We identified that a working distance of 2.5 cm provides the optimal balance between stitching success rate and spatial resolution, while a 1/3 overlap ratio minimizes cumulative drift errors better than higher overlap settings. These findings establish a practical guideline for clinicians using handheld devices.
Although the proposed 2D framework inherently involves geometric distortions such as arch straightening, limiting its application in precision metric tasks like prosthetics, it offers substantial value as a cost-effective tool for dental screening, patient education, and telemedicine. Future research will focus on extending this framework to 3D reconstruction techniques, such as Neural Radiance Fields (NeRF) or 3D Gaussian Splatting, to recover accurate depth information and address the geometric limitations of 2D projection.