


Abstract
(1) Background: Supraglottic airway devices (SAD) have been used in children and adolescents undergoing adenotonsillectomies under general anesthesia. This systematic review and meta-analysis investigate the safety and efficacy of using SADs when compared to an endotracheal tube (ETT). (2) Methods: After registering with PROSPERO, databases like PubMed, Scopus, OviD, CINAHL, and Cochrane Library were searched using relevant keywords from the year 2000. We used RoB-2 for risk-of-bias assessment, GRADE for assessing the quality of evidence, RevMan 5.2 for qualitative meta-analysis, and trial sequential analysis (TSA) to corroborate the significant findings of meta-analysis. (3) Results: Out of 200 studies, 5 randomized-controlled trials fulfilled inclusion criteria. The quality of evidence was moderate for laryngospasm, low for airway device failure, and very low for recovery time. The incidence of laryngospasm was comparable between SADs and ETT (RR: 0.80, 95% CI-0.36, 1.80, p = 0.59). The incidence of airway device failure was significantly higher with SADs than ETT (RR: 11.29, 95% CI: 2.73, 46.66, p = 0.0008). The postoperative recovery time was significantly less with SADs than with ETT use (MD: −4.33, 95% CI: −5.28, −3.39, p < 0.0001), which was confirmed by the TSA. (4) Conclusions: The results of this review suggests that use of SADs can provide a lesser postoperative recovery time and comparable incidence of laryngospasm, with a higher incidence of failure of SAD when compared to ETT. Use of SAD for pediatric and adolescent adenotonsillectomies should be individualized based on patient characteristics, and on the expertise of the anesthesiologist and the surgeons involved.
1. Introduction
Adenoidectomy and tonsillectomy, either alone or as combined surgeries, are commonly performed surgical interventions in the pediatric population that necessitate meticulous airway management to ensure uninterrupted ventilation and to secure the airway during the surgery. Endotracheal intubation with an appropriate-sized tube has been the cornerstone for airway management during these surgeries [1,2,3]. Supraglottic airway devices (SADs), such as the laryngeal mask airway (LMA) and its various pediatric variations, when used as an airway adjunct, provide effective ventilation by forming a seal above the glottis, thereby obviating the need for tracheal intubation. The use of SAD reduces the incidence of trauma to the airway structures, subsequently avoiding the risk of postoperative complications [4,5]. A quantitative meta-analysis concluded that the use of SADs in pediatric anesthesia decreases the number of respiratory complications [6].
Recently, SAD has been used effectively with considerable safety as an alternative to endotracheal intubation in pediatric and adolescent patients undergoing adenotonsillectomy. Various studies have attested that SADs are less irritating to the otherwise reactive airways of these patients, thus reducing the incidence of perioperative respiratory adverse events like bronchospasm, laryngospasm, and incessant coughing postoperatively [7,8]. While the use of SADs in pediatric adenotonsillectomy is gaining popularity, anesthesiologists must be meticulous with patient selection, the type of SAD used, procedural technique, and ongoing monitoring. Appropriate sizing, correct placement, and vigilant perioperative monitoring are paramount to ensuring the efficacy and safety of SADs for this surgical indication [9,10].
The objective of this review was to investigate the safety and feasibility of using various SADs in pediatric and adolescent patients undergoing adenoidectomy, tonsillectomy, or both. We also aimed to evaluate other outcomes like success rate, various periods like induction time, recovery time, and time spent in the recovery room.
2. Materials and Methods
This review adhered to the protocol established by the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines, which comprise a checklist of 27 essential points. This systematic review was prospectively registered with PROSPERO (https://www.crd.york.ac.uk/PROSPERO/ (accessed on 27 December 2023)) with the registration number CRD42023494137.
2.1. Search Strategy
Starting from January 2000 until December 2023, we searched PubMed/Medline, Cochrane Library (CENTRAL), CINAHL, OViD, and Scopus using relevant keywords for randomized-controlled trials with the following keywords: supraglottic airway, laryngeal mask airway, adenoidectomy, tonsillectomy, adenotonsillectomy, pediatric, and adolescent. A detailed search strategy is presented in Table 1. Articles without a control group or not having the outcomes of interest were excluded from the analysis.
Table 1.
Search details for various databases.
2.2. Eligibility Criteria
We used a structured Population, Intervention, Control, Outcome, Study (PICOS) design to select relevant studies. Only RCTs were included and studies not in English, animal studies, studies with unavailable full texts, systematic/literature/scoping reviews, case reports/series, editorials, and conference abstracts were excluded.
Population: all pediatric and adolescent patients undergoing adenoidectomy, tonsillectomy, or adenotonsillectomy were included.
Intervention: use of a SAD as an airway adjunct for general anesthesia.
Control: use of an endotracheal tube for general anesthesia.
Outcome: safety and efficacy of SAD for adenotonsillectomy.
Study: randomized-controlled studies.
2.3. Data Extraction
The initially identified studies were screened by two authors (AN and NB) according to the inclusion and exclusion criteria. If the two authors disagreed about the inclusion of the study, another author (UD) was asked to settle the disagreement. The primary outcome was the incidence of laryngospasm. Secondary outcomes were the incidence of airway device failure, recovery time, time spent in the operating room after surgery, and other adverse events like aspiration, regurgitation, and bronchospasm.
2.4. Data Collection
Two authors conducted data extraction for each included article and tabulated details like authors, year, participants, sample size, type of SAD used, outcomes, interventions, measurement instruments, key findings, and conclusions. The selection of studies used in the results was independently performed by two researchers (AN and UD) through the review of titles and abstracts.
2.5. Methodological Assessment
The methodological quality of the included studies was independently evaluated by two authors (AN and NB) as recommended by the Cochrane Intervention System Evaluation Manual (Cochrane Handbook for Systematic Reviews of Interventions) [11].
If the two researchers disagreed about the methodological assessment, another researcher (SSM) was involved in concluding. The methodological assessment comprised random sequence generation (selective bias), allocation concealment (selective bias), blinding of participants and personnel (performance bias), blinding outcome assessment (detection bias), incomplete outcome data (attrition bias), selective reporting (reporting bias), and other biases.
2.6. Strength of Quality across All the Trials
The overall methodological quality of evidence across pooled outcomes was assessed using the Grading of Recommendation, Assessment, Development, and Evaluation (GRADE) guidelines [12]. Study design, bias risk, consistency, directness, precision, and other factors (publication bias, large effect, confounding) were taken into account when determining the evidence for pooled outcomes. The definition of the certainty of the evidence was as follows: (1) high-quality additional research is highly unlikely to alter the confidence in the estimate of effect; (2) moderate-quality additional research is likely to significantly affect the estimate’s confidence and may alter it; and (3) low-quality additional research is highly likely to alter the estimate; or (4) extremely poor quality: the estimate is uncertain.
2.7. Quantitative Meta-Analysis
Meta-analysis was performed using RevMan 5.2 [13]. Relative risk (RR) and the 95% confidence interval (CI) were used for binary variables. For continuous variables, mean difference (MD) and 95% CI were used. The results are presented as forest plots, RR or MD, and 95% CI, with p < 0.05 being regarded as statistically significant. The χ2 and I2 tests were performed for clinical heterogeneity in the included studies, and p < 0.10 and I2 > 50% showed that χ2 had statistical differences. A fixed-effects model was utilized if the study results showed low heterogeneity (p > 0.10, I2 < 50%). The random-effects model was utilized for the meta-analysis in all other cases [11]. To investigate the reasons for high heterogeneity, subgroup analysis and sensitivity analysis were performed, by excluding one study at a time.
2.8. Publication Bias
Funnel plots of effect sizes against standard errors for outcomes were examined for asymmetry if there were more than 10 studies that fulfilled the inclusion criteria [14]. The Egger bias test was used as a corresponding statistical test, with p < 0.10 indicating asymmetry [15].
2.9. Sensitivity Analysis
To verify that the pooled effect sizes were not the result of a single study dominating, data from each study were successively removed, and the remaining data were then reanalyzed to assess the robustness of the pooled estimates for outcomes that included data from three or more studies.
2.10. Trial Sequential Analysis (TSA)
To determine whether our findings were conclusive, TSA was performed on the data using the TSA Module version 0.9.5.10 (Copenhagen trial unit, Denmark, Copenhagen) to calculate the required information size (RIS). The cumulative Z curve was produced using a random-effects model and the DerSimonian–Laird (DL) technique. The goal of TSA was to maintain a 5% overall risk of a type I error [16,17].
3. Results
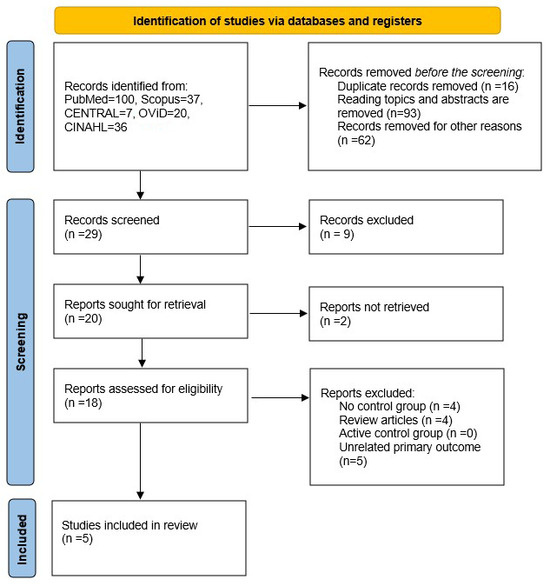
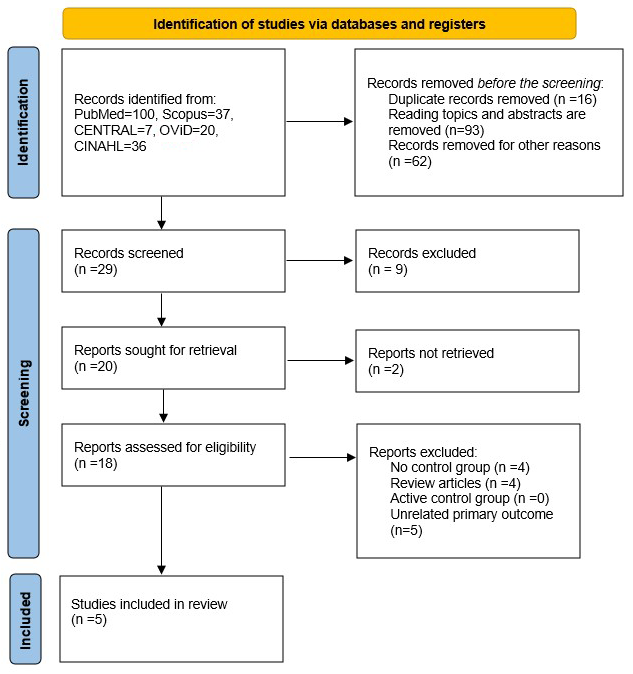
A total of 200 articles were identified using the inclusion criteria mentioned above. The details are available in Figure 1. After removing duplicates, and excluding articles that were not relevant, 29 titles were screened, out of which 9 were excluded. From the remaining 20 articles, 2 articles were not retrieved as they were found to not be relevant. Out of the remaining 18 articles, 13 articles were excluded (4 review articles, 4 articles with no control group, and 5 articles with unrelated primary outcome). Finally, 5 articles (RCTs) were selected for a qualitative systematic review and a quantitative meta-analysis [18,19,20,21,22]. Study characteristics and outcome details are summarized in Table 2 and Table 3.
Figure 1.
PRISMA flowchart.
Table 2.
Study characteristics.
Table 3.
Outcome data in all the included studies.
3.1. Risk-of-Bias Assessment
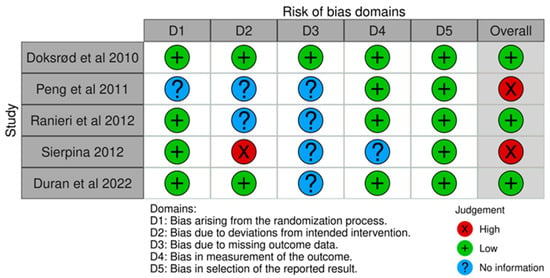
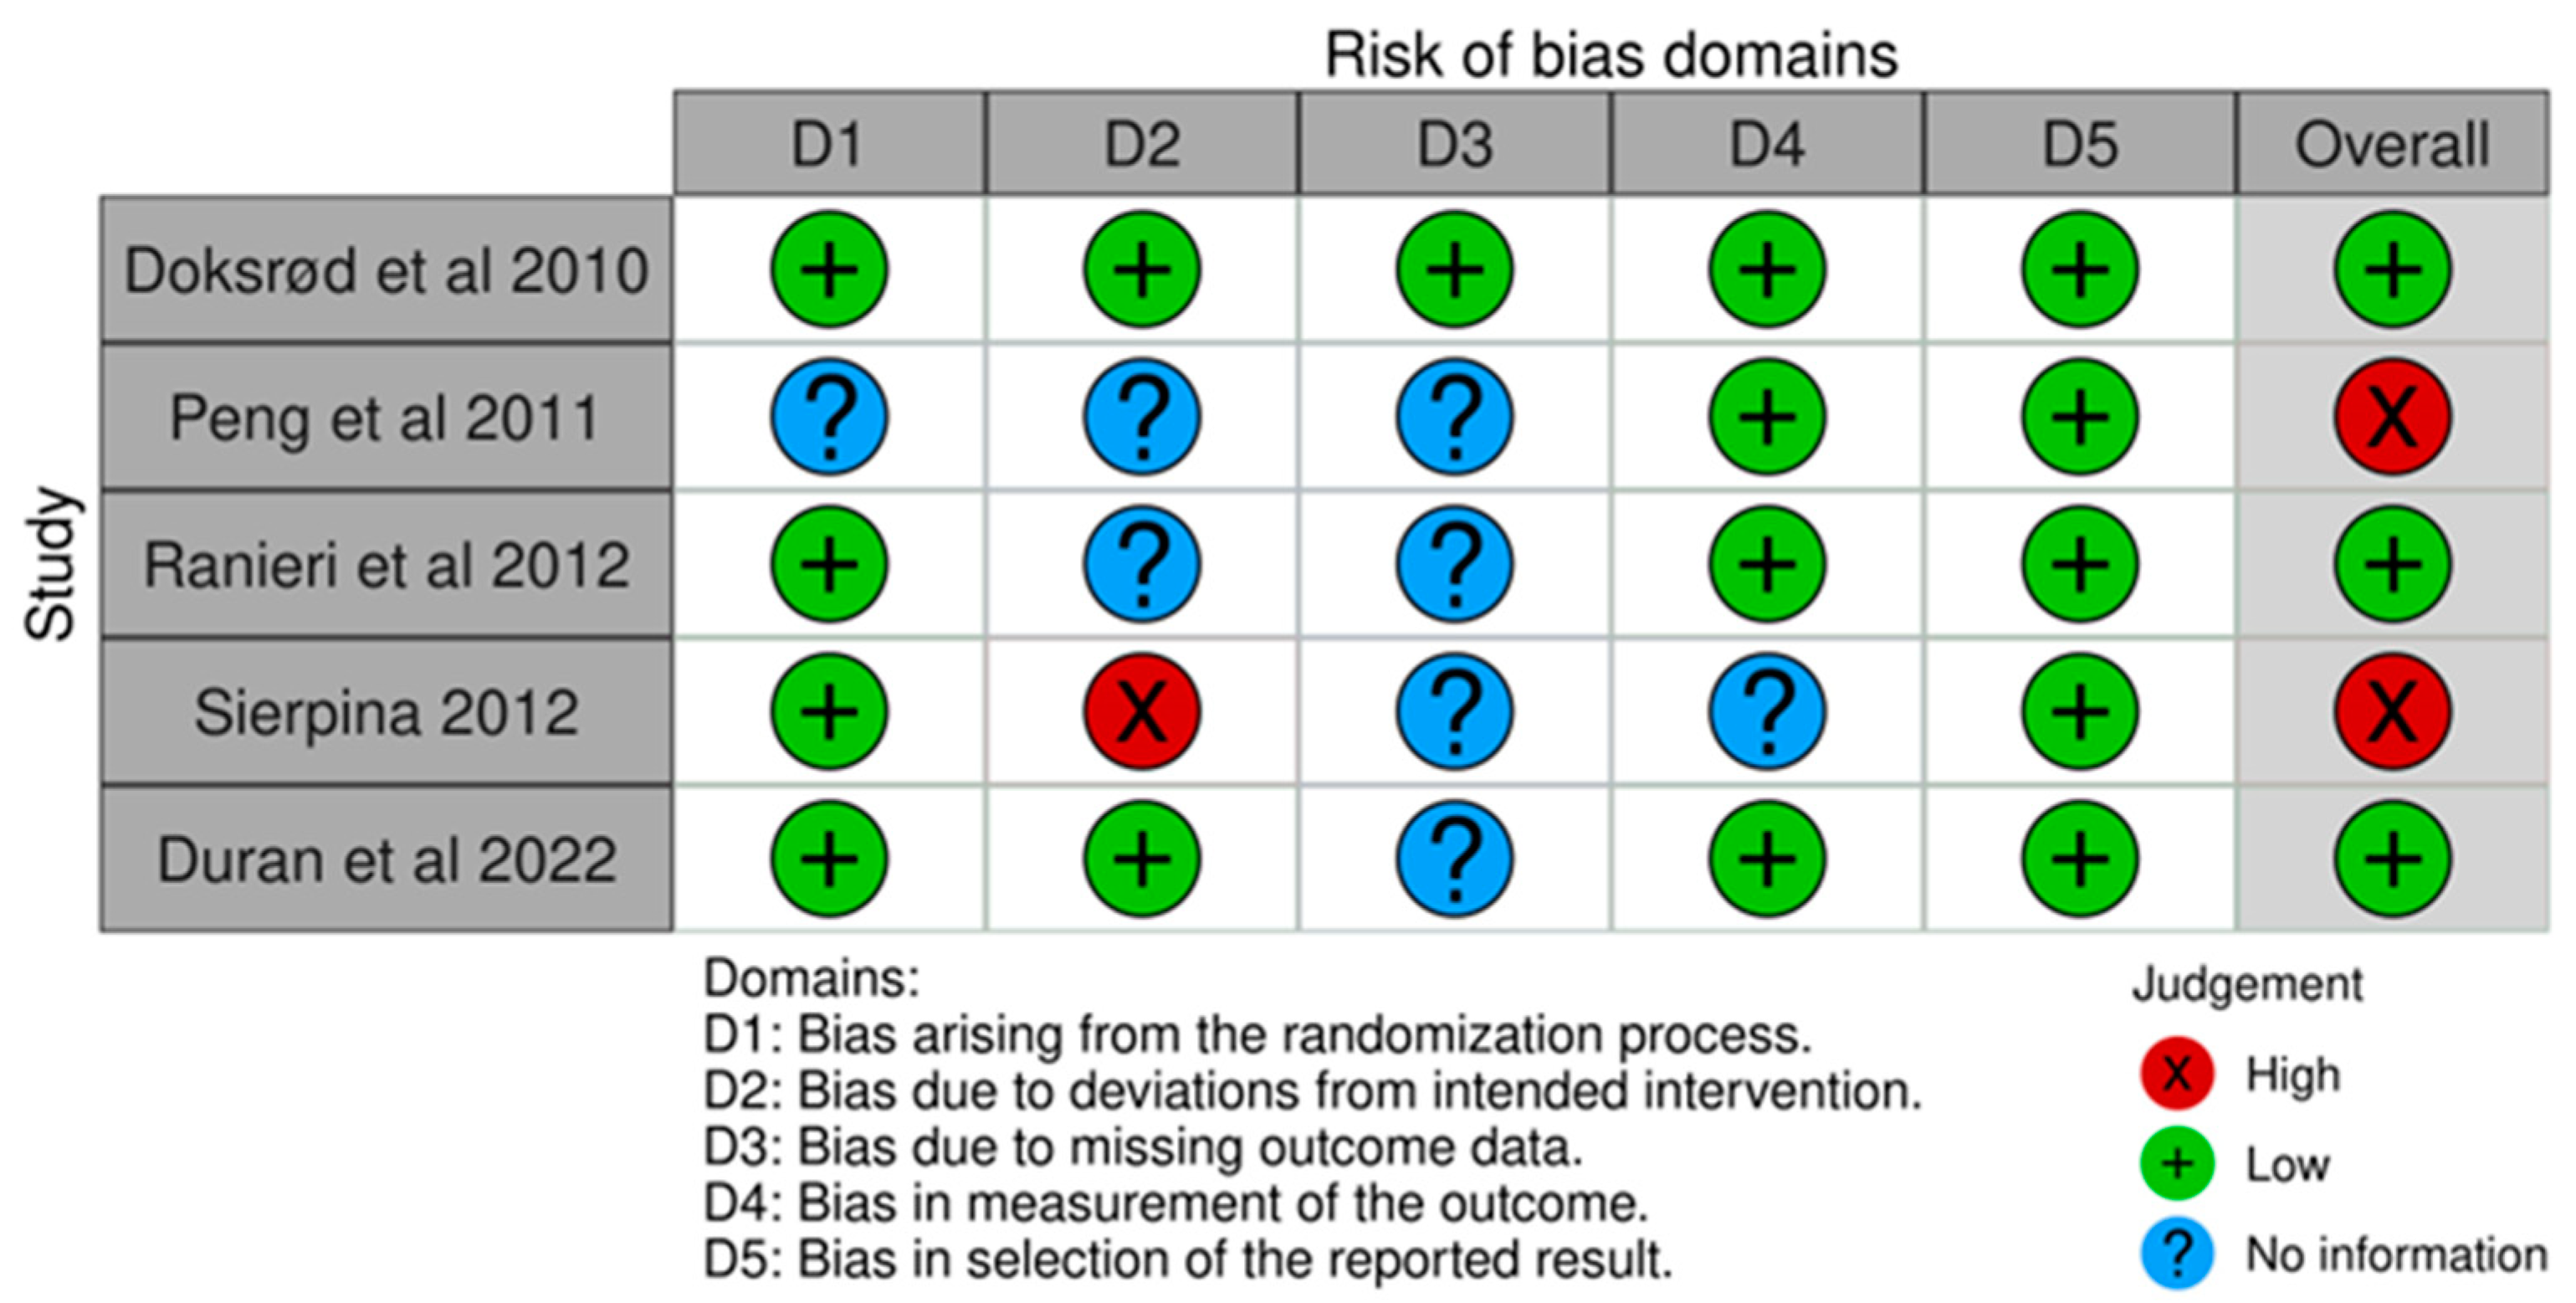
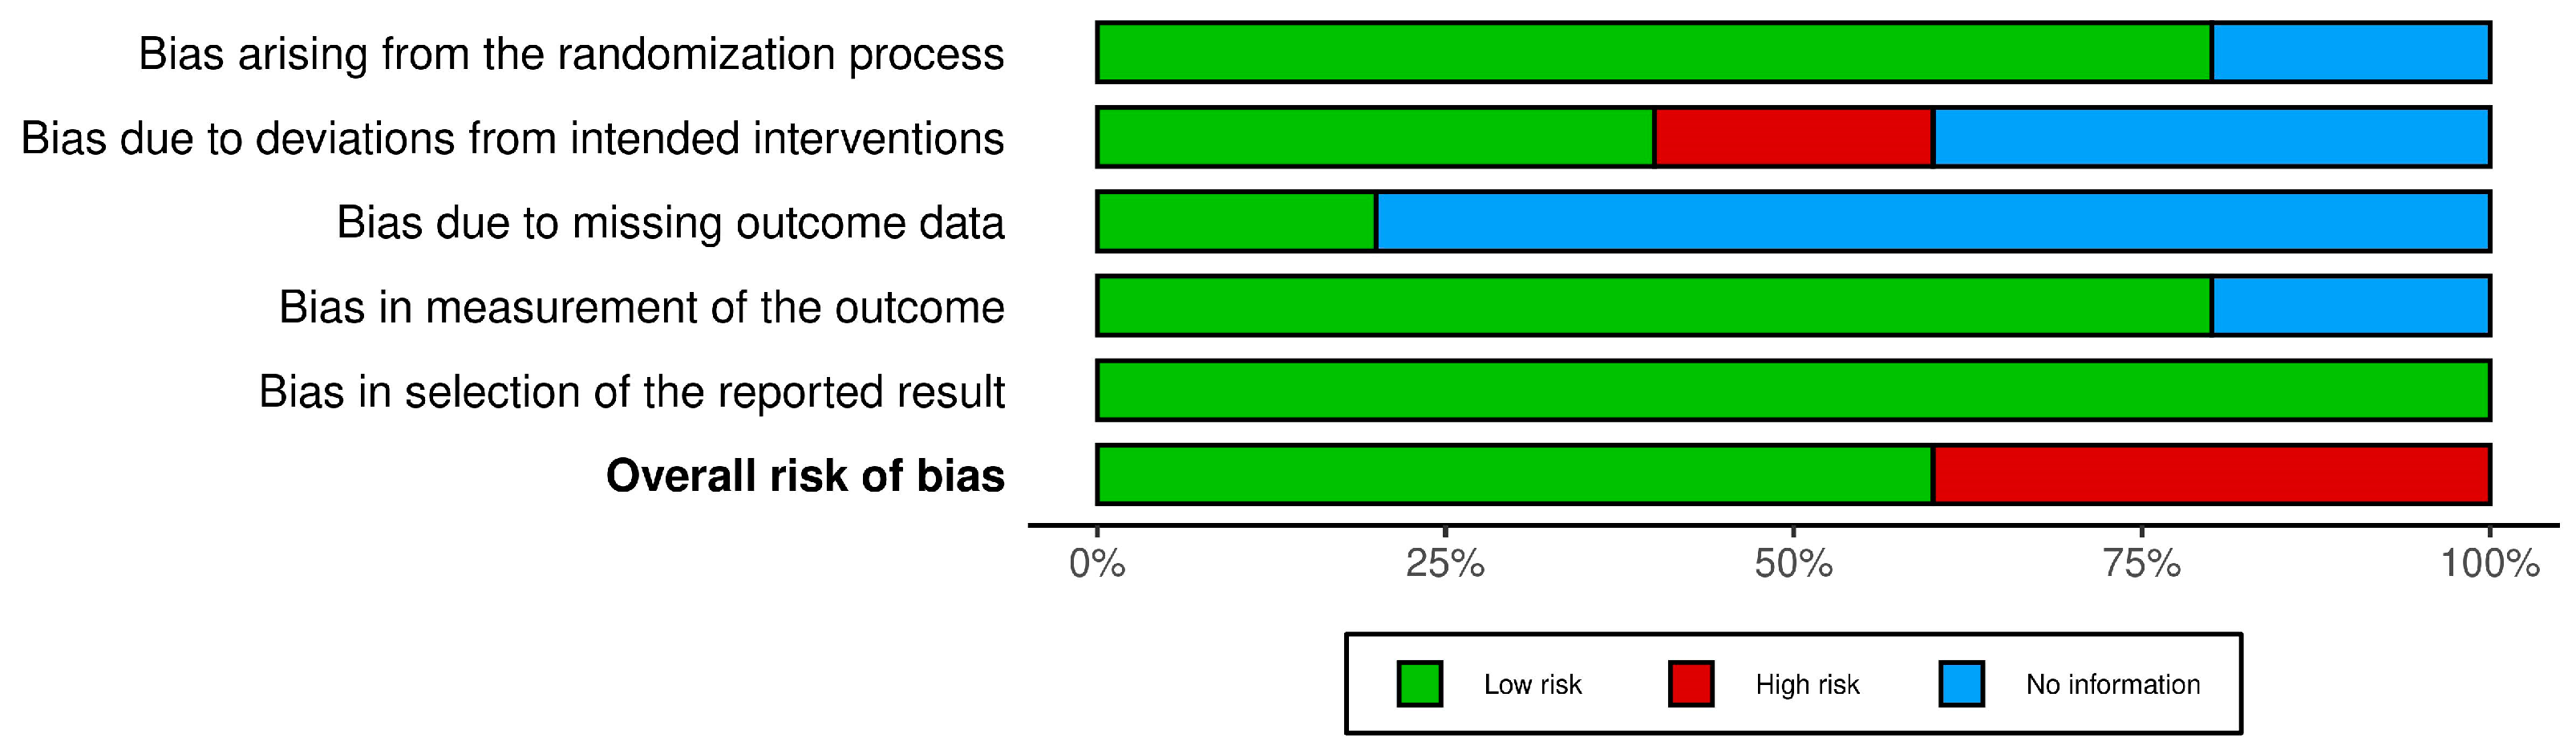
The risk of bias within the trials according to ROB2 is depicted in Figure 2 (traffic light plot) and Figure 3 (summary plot). The bias from the randomization process was low in four studies [18,20,21,22] and there was no information in one study [19]. Bias due to deviations from intended interventions (allocation concealment) was low in studies [18,22], high in one study [21], and there was no information in two studies [19,20]. Bias arising due to missing outcome data was low in one study [18] and there was no information in four studies [19,20,21,22]. Bias in the measurement of outcome was low in four studies [18,19,20,22] and there was no information in one study [21]. Bias arising due to the selection of reported results was low in all five studies [18,19,20,21,22].
Figure 2.
Traffic light plot [18,19,20,21,22].
Figure 3.
Summary plot.
3.2. Quality of Evidence
Using the GRADE system, three outcomes were assessed for the quality of evidence (Table 4). The quality of evidence was moderate for laryngospasm, low for airway device failure, and very low for recovery time.
Table 4.
GRADE strength of evidence.
3.3. Primary Outcome Meta-Analysis
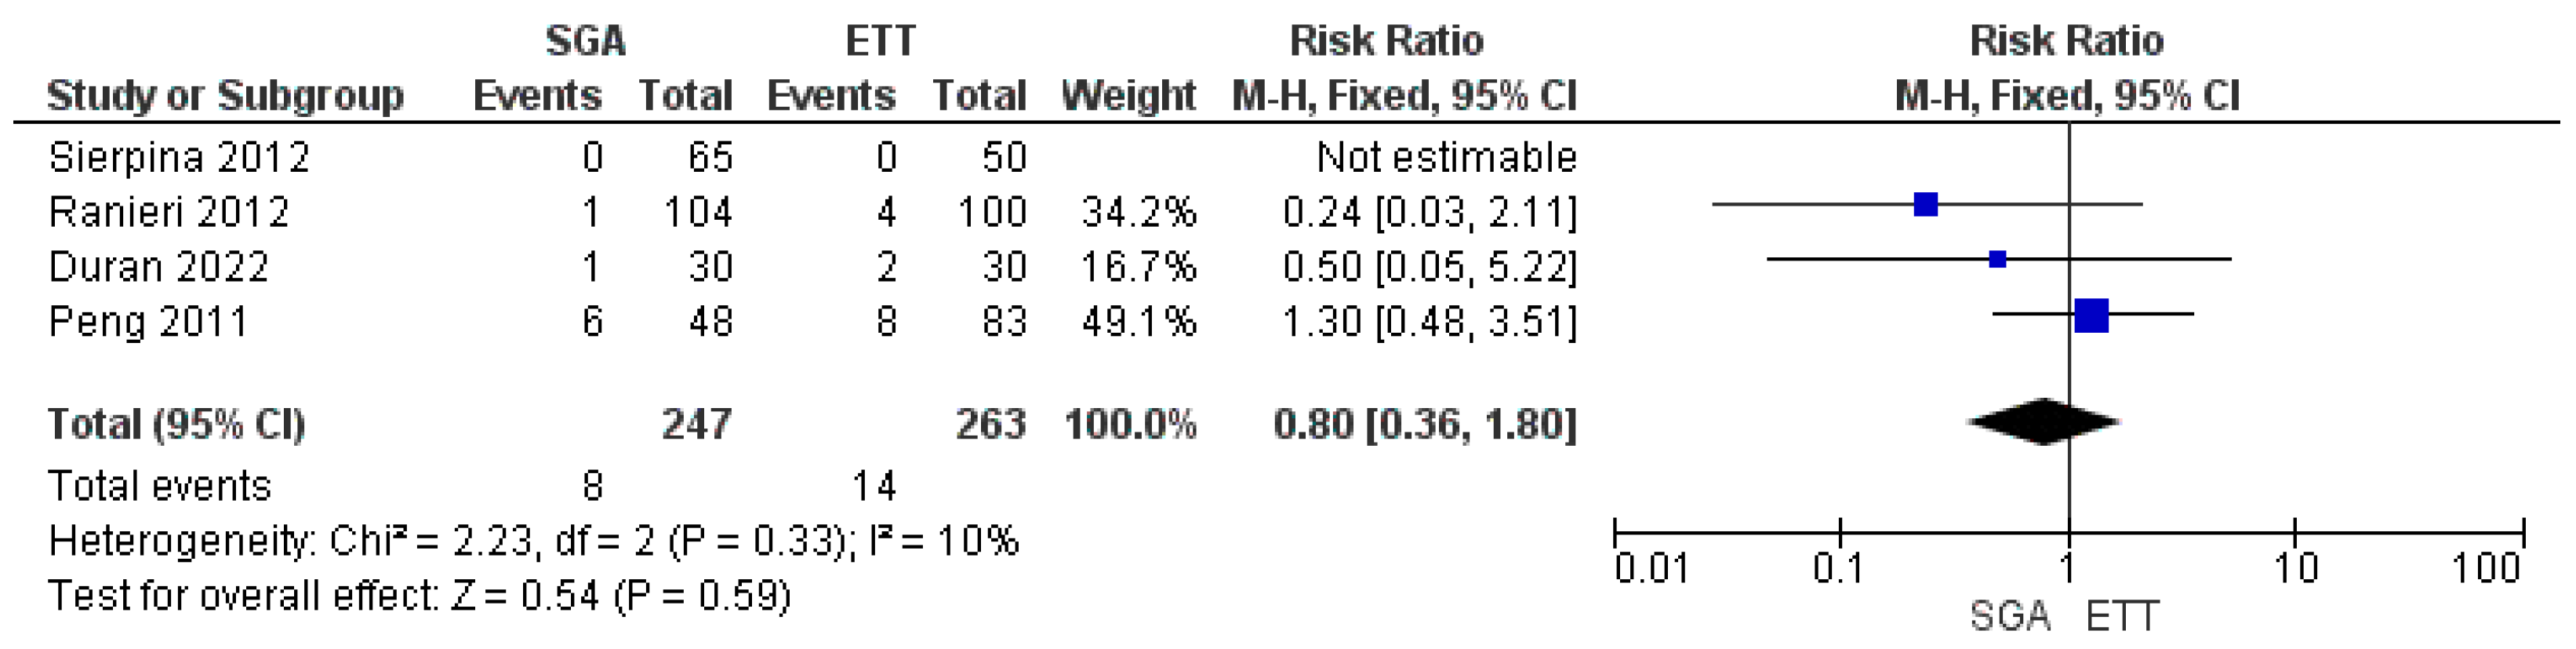
Four studies reported laryngospasm as an outcome (247 patients in the SAD group and 263 patients in the ETT group) [19,20,21,22]. A pooled analysis revealed that the incidence of laryngospasm was comparable between the SAD group and the ETT group (RR: 0.80, 95% CI-0.36, 1.80, p = 0.59) (Figure 4). A fixed-effect model revealed low heterogeneity (I2 = 10%) [GRADE = moderate].
Figure 4.
Forest plot showing the comparison of the incidence of laryngospasm between the use of SAD and ETT in children undergoing adenotonsillectomy [19,20,21,22].
3.4. Meta-Analysis of Airway Device Failure
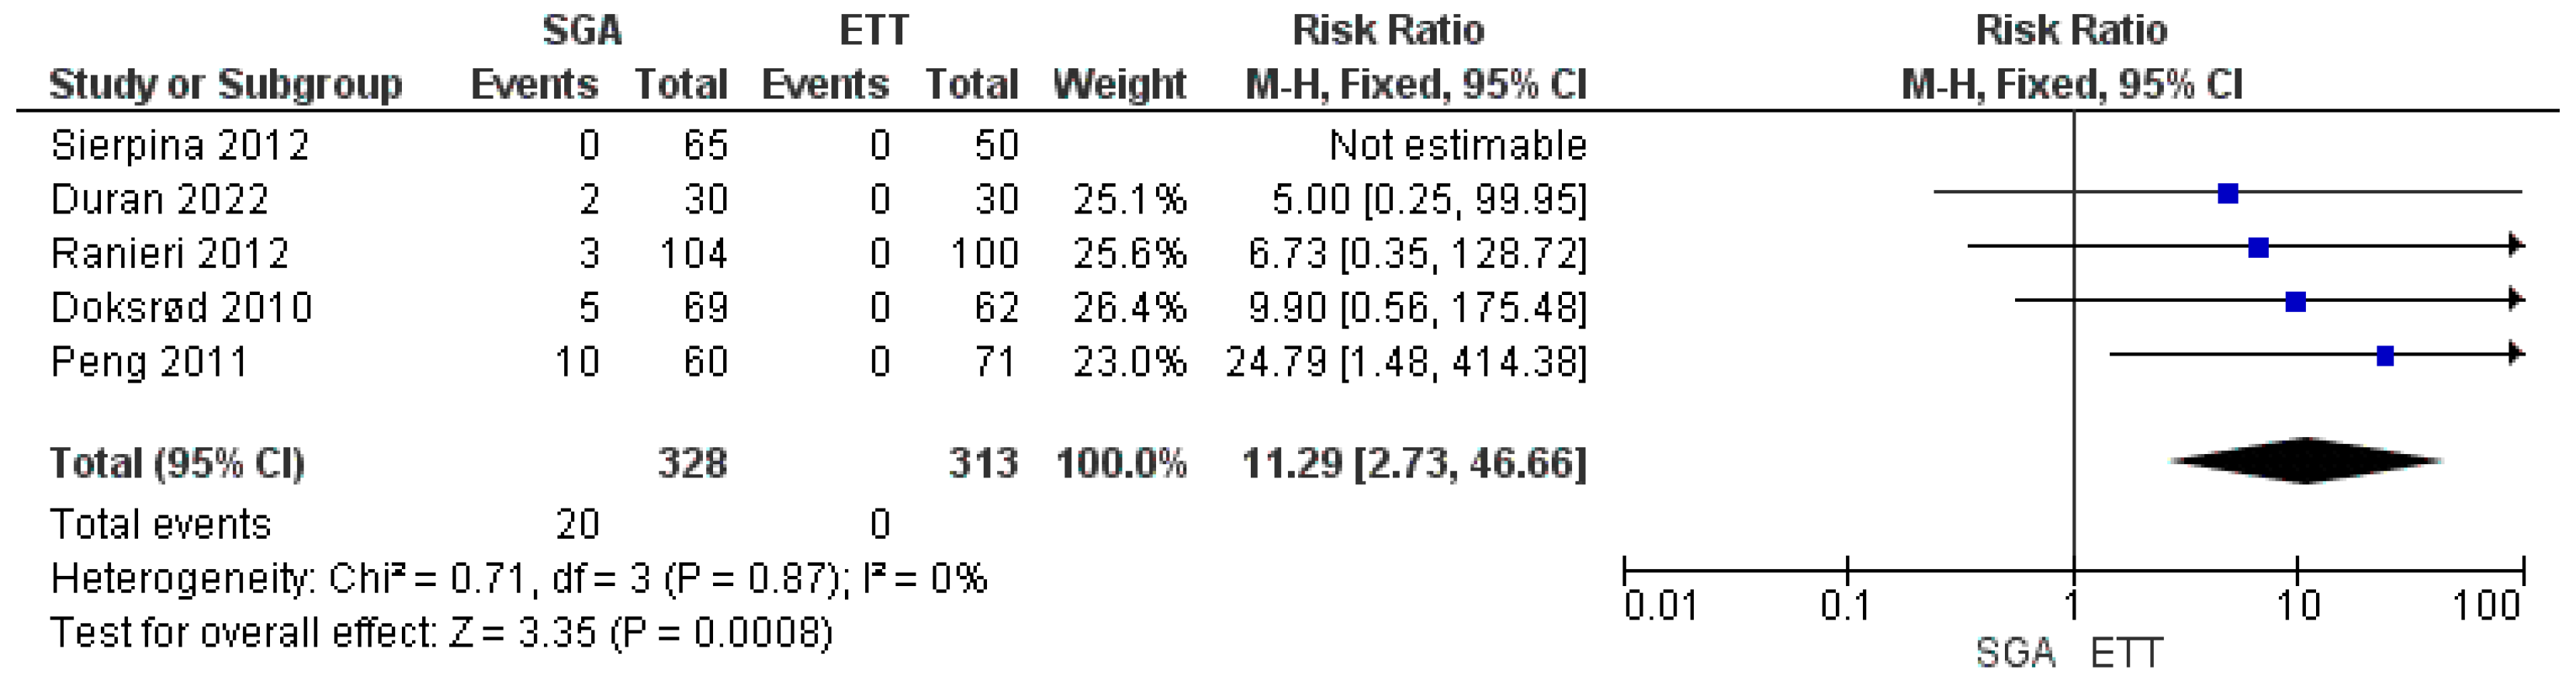
Five studies reported airway device failure, requiring conversion to ETT (328 patients in the SGA group and 313 patients in the ETT group) [18,19,20,21,22]. A pooled analysis revealed that the incidence of airway failure was high in the SAD group (RR: 11.29, 95% CI: 2.73, 46.66, p = 0.0008) (Figure 5). A fixed-effect model revealed no heterogeneity (I2 = 0%) [GRADE = low].
Figure 5.
Forest plot showing the comparison of the incidence of airway device failure between the use of SAD and ETT in children undergoing adenotonsillectomy [18,19,20,21,22].
3.5. Meta-Analysis of Postoperative Recovery Time
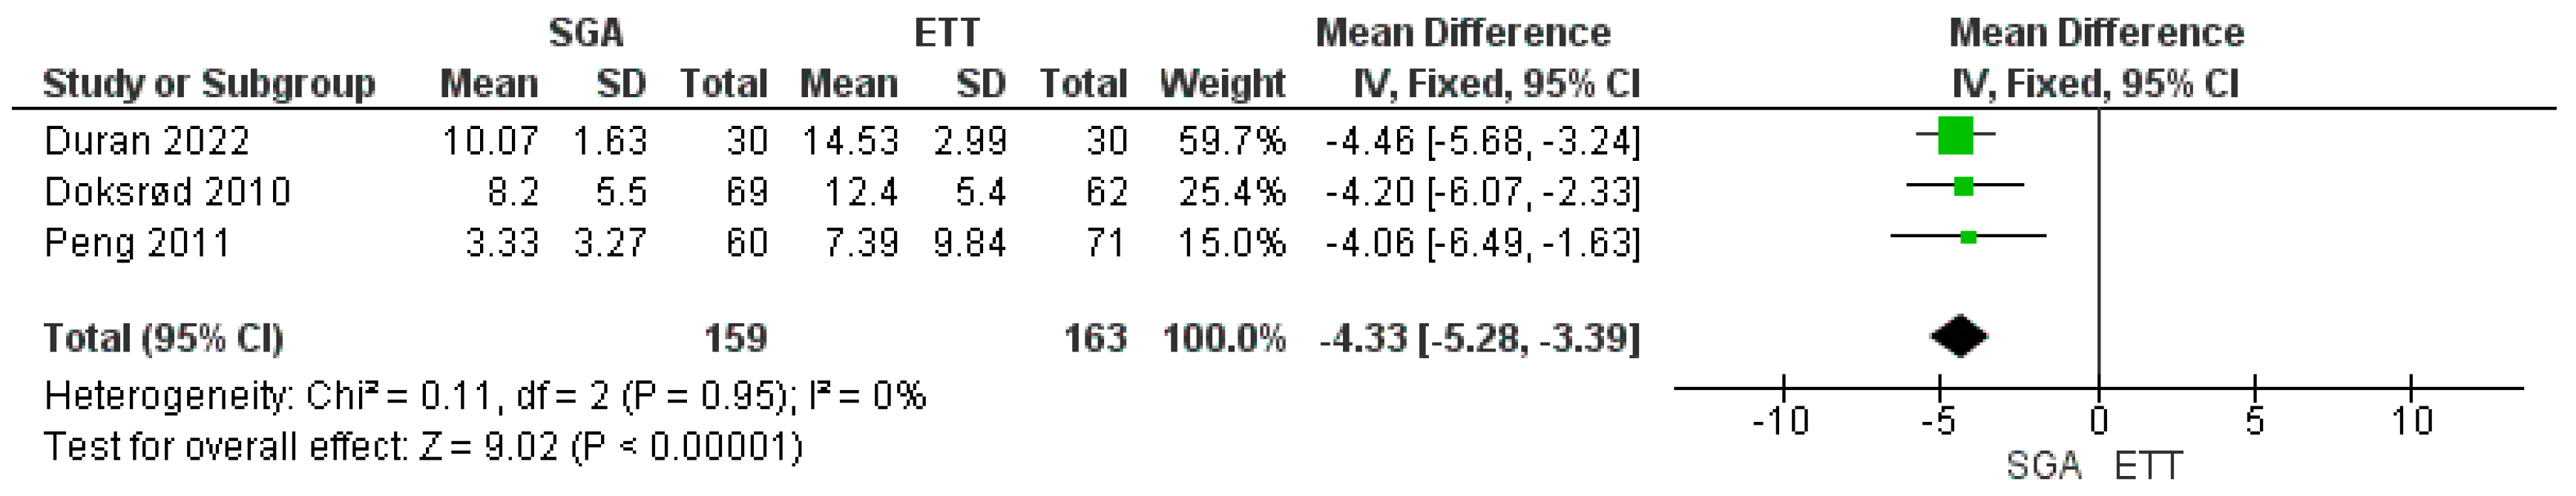
Three studies compared recovery times (159 patients in the SAD group and 163 patients in the ETT group) [18,19,22]. The overall recovery time was significantly less in the SAD group when compared to patients in the ETT group (MD: −4.33, 95% CI: −5.28, −3.39, p < 0.0001) (Figure 6). A fixed-effect model revealed no heterogeneity (I2 = 0%) [GRADE = very low].
Figure 6.
Forest plot showing the comparison of postoperative recovery time between the use of SAD and ETT in children undergoing adenotonsillectomy [18,19,22].
3.6. Other Outcomes
Several studies reported other perioperative outcomes. Intubation time and surgical view were reported by Duran et al. [22]. Surgical time, total anesthesia time, and extubation time were reported by Peng et al. [19]. Oxygen saturation was reported by Ranieri et al. [20] and Duran et al. [22]. Hemodynamics (heart rate) and end-tidal carbon dioxide were reported by Doksrød et al. and Duran et al. [18,22]. The duration of surgery was reported by Sierpina et al. and Duran et al. [21,22]. Pooled analysis was not performed for these outcomes as the number of studies reporting them was less.
As the number of included studies was five (less than 10), publication bias was not assessed and therefore funnel plots were not created.
3.7. TSA
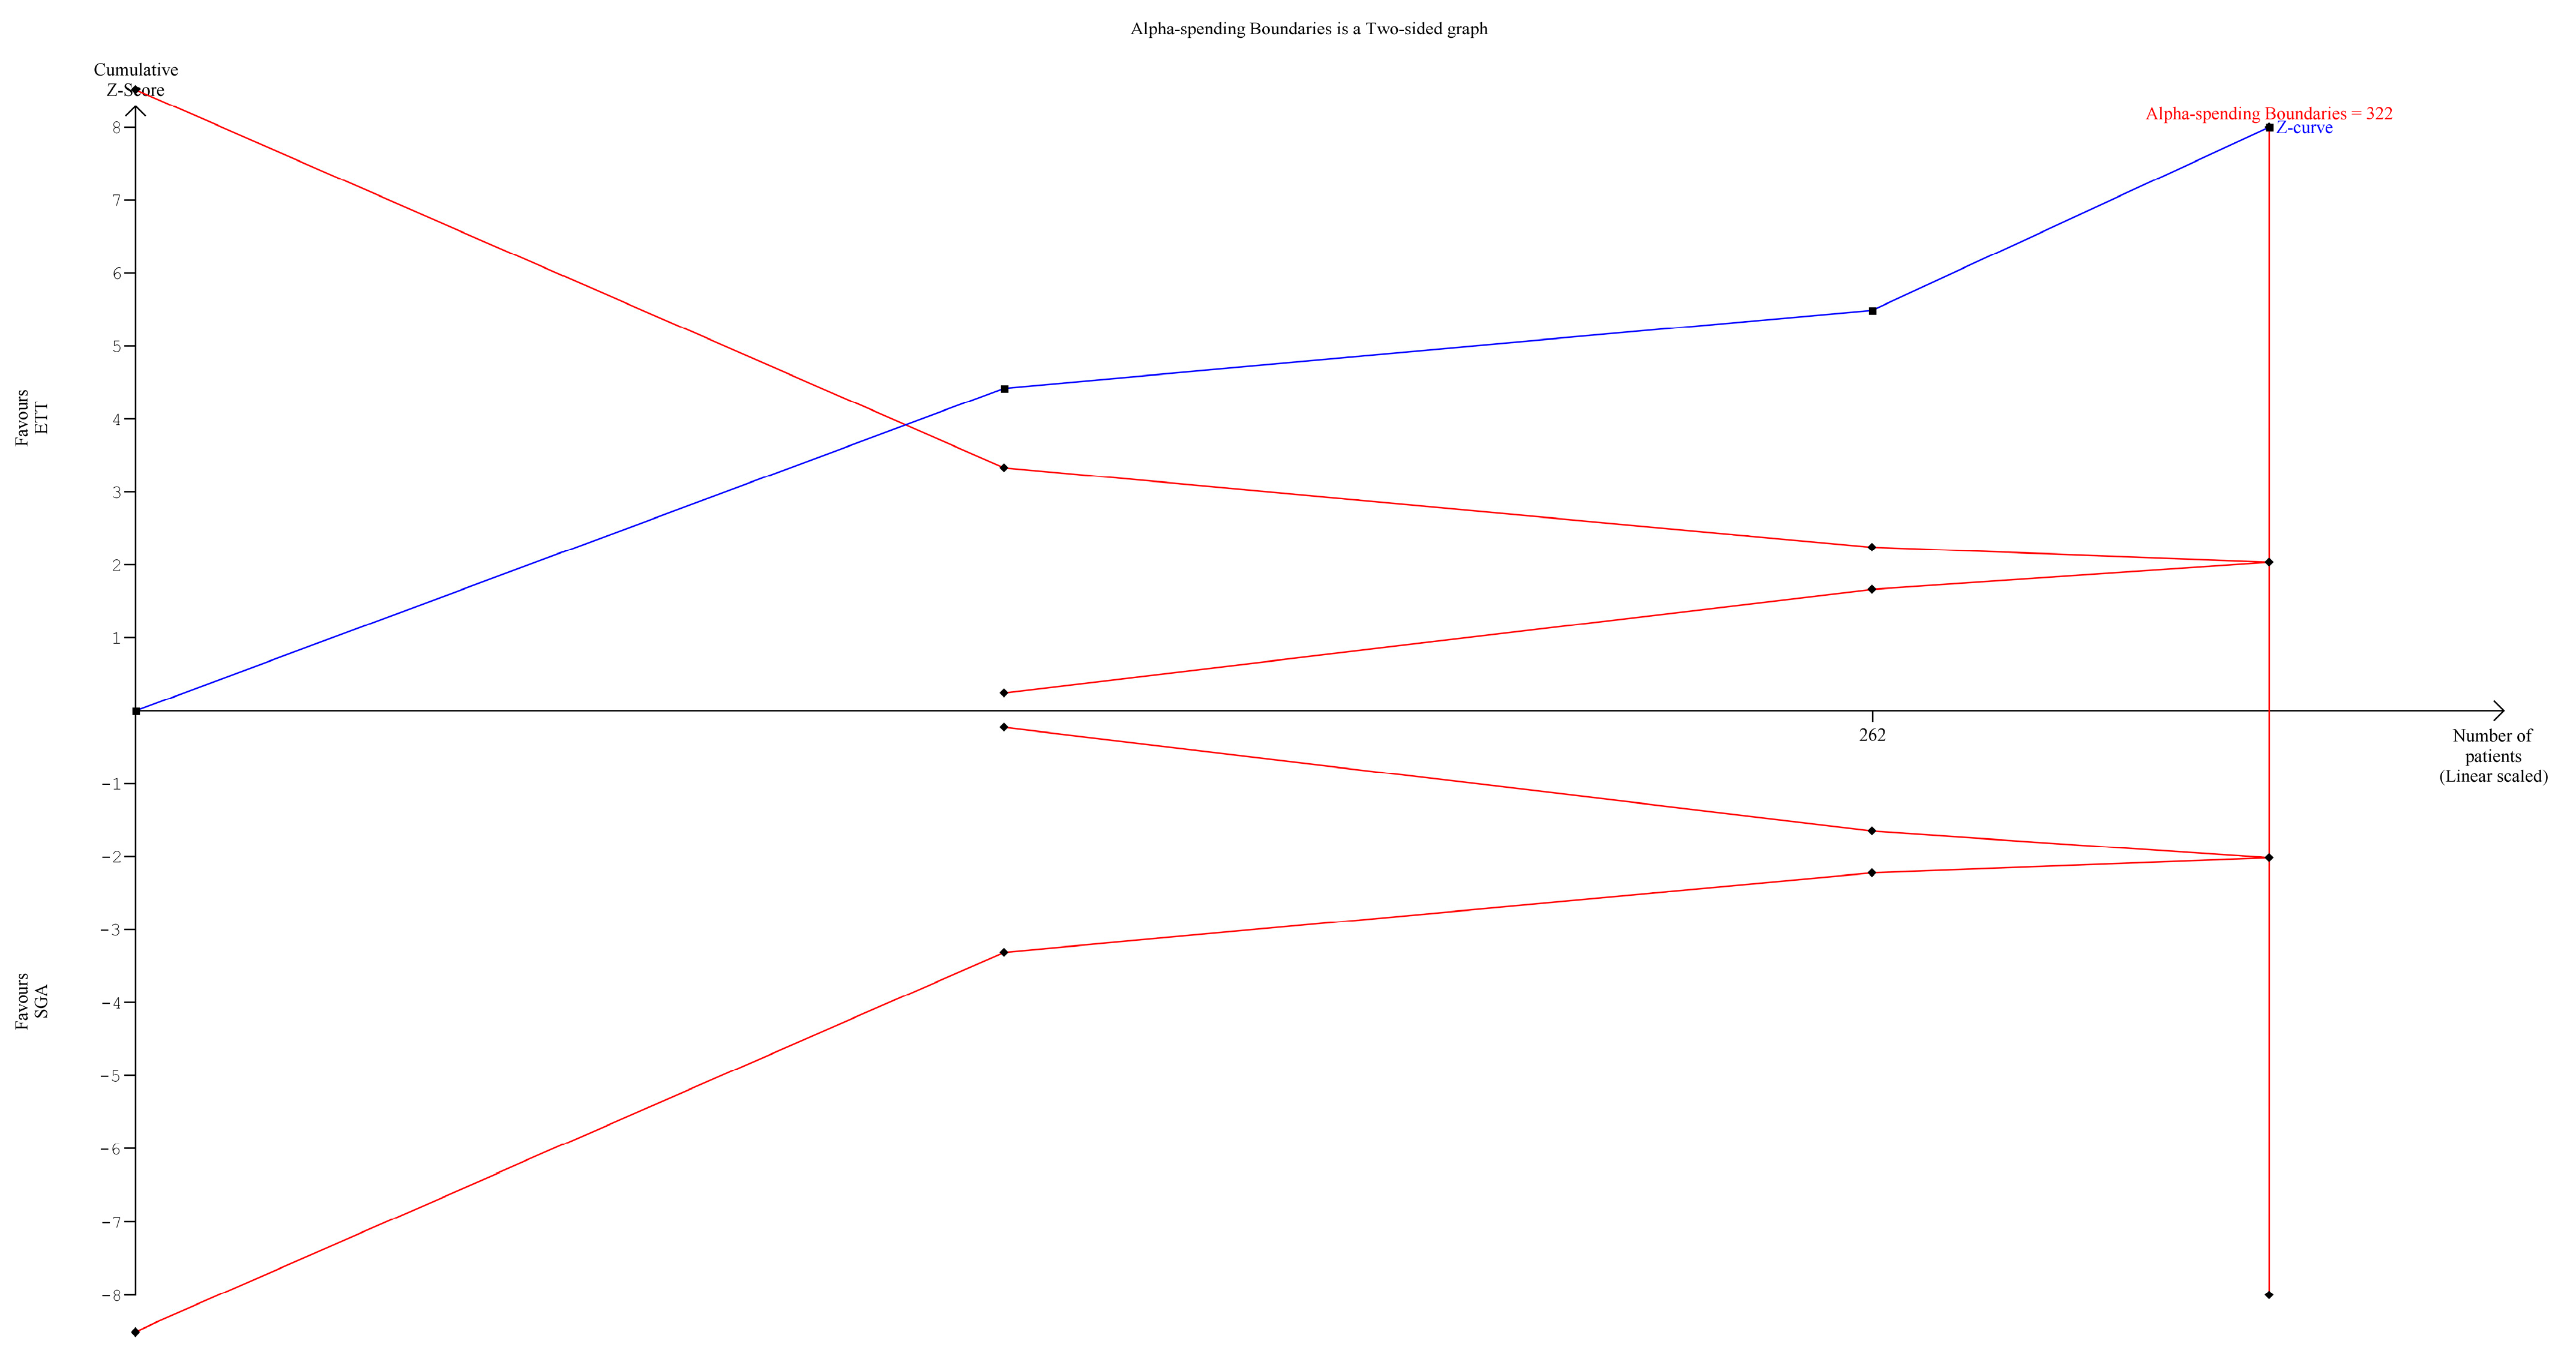
TSA was performed only for postoperative recovery time. For the primary outcome, i.e., laryngospasm, the incidence was comparable in both groups. For device failure, the pooled analysis was significant, but as the values were zero in the ETT group, TSA could not be performed. The cumulative z-curve crossed any of the two boundaries, which means that the duration of recovery time was significantly less in the SAD group than in the ETT group (Figure 7).
Figure 7.
TSA showing the comparison recovery times between the use of SAD and ETT in children undergoing adenotonsillectomy.
4. Discussion
Summary of Results
This systematic review and meta-analysis investigated the safety and efficacy of using various SADs in children and adolescents undergoing adenotonsillectomy when compared to ETT. A pooled analysis revealed that the incidence of laryngospasm was comparable with the use of either of the airway adjuncts, with a moderate level of evidence. The failure rate with SADs, i.e., conversion to ETT, was considerably high. The failure of the airway in the ETT group was zero because an ETT is a definitive airway and is unlikely to fail. The overall recovery time with the use of SAD was significantly less.
Airway management is of paramount importance in pediatric anesthesia [23,24]. This responsibility is even more crucial when the anesthesiologists are sharing the airway with the surgeons, as during adenotonsillectomies. These children have a higher propensity of having respiratory tract infections, mostly viral, and even if they do not have fever, the symptoms like cough and running nose are persistent. Such patients are more prone to perioperative respiratory adverse events (PRAE) like laryngospasm, bronchospasm, and desaturation [25].
The use of SADs in various pediatric surgeries became popular as it involves reduced airway stimulation, facilitates faster recovery, and leads to lesser hemodynamic changes, especially during intubation and extubation [26,27]. In a systematic review and meta-analysis investigating the safety and efficacy of LMA in pediatric laparoscopic hernia surgeries, Yang et al. concluded that the use of LMA is safe and leads to lesser anesthesia and recovery time and hence is an appropriate option when compared to ETT [28]. The use of a non-depolarizing muscle for placing LMA is not necessary and depends on the type of surgery and the comfort of the anesthesiologist [29,30]. However, Wu et al. suggested the use of non-depolarizing muscle relaxants can improve surgical conditions and reduce the incidence of adverse events like laryngospasm and bronchospasm [31].
Although many clinicians have started using SAD for various pediatric surgeries, its use in adenotonsillectomies is still considered controversial. Lalwani et al. retrospectively reviewed medical records of 1199 children who underwent adenotonsillectomy from 2003 to 2006, using both LMA and ETT [32]. On analysis, the authors concluded that the use of LMA for pediatric adenoidectomies is linked to a higher rate of complications, primarily from airway obstruction that occurs after LMA insertion or mouth gag placement. They also mentioned that in tonsillectomy, careful patient selection, insertion technique, and avoidance of controlled ventilation may reduce the risk of LMA failure. Surgeons’ ability to operate around the LMA may significantly impact the failure rate.
In a study involving 100 patients from 10 to 35 years undergoing adenotonsillectomy randomized for armored LMA and ETT as the definitive airway for surgery, the authors concluded that an armored laryngeal mask is reliable for performing adenotonsillectomy, provides adequate surgical access for adenotonsillectomy, and is also associated with a lower occurrence of respiratory adverse events like cough, bronchospasm and stridor at recovery. Patients with an armored LMA even demonstrated stable hemodynamics when compared to ETT [33].
In a prospective audit by Thorning et al. comprising 366 day-case pediatric ENT surgeries with LMA, the overall conversion from LMA to ETT was 4.3% (15 patients) [34]. Other than transient desaturation, the rest of the patients were successfully managed over an LMA. In a study comprising 139 pediatric patients (110 LMA, 27 with ETT, and 2 patients with LMA changed to ETT due to ventilatory difficulties) undergoing adenoidectomy, Boroda et al. attempted to investigate the success rate of LMA in these patients as an airway adjunct [35]. The authors concluded that the use of LMA is safe, without any significant adverse events, and also contributes to a reduced operating room time.
Gravningsbråten et al. reported their experience of 1126 pediatric patients (less than 16 years) undergoing office-based adenotonsillectomy using LMA [7]. In this series, one patient was reintubated because of atelectasis, and in six patients the LMA was replaced with ETT due to inadequate ventilation. Two patients underwent reoperation and eight patients were readmitted (two for reoperation and six for observation). They concluded that adenotonsillectomy can be safely performed in an office-based setting using LMA.
In another RCT involving 290 pediatric patients (less than 16 years) undergoing tonsillectomies, Ramgolam et al. compared the occurrence of perioperative respiratory adverse events during the emergence and post-anesthesia care unit phases of anesthesia [36]. On analysis, the authors concluded that there was no evidence for a difference in the timing of the LMA removal on the incidence of respiratory adverse events during the emergence and post-anesthesia care unit phases. However, in the post-anesthesia care unit solely, awake removal was associated with significantly more respiratory adverse events than deep removal. In a retrospective study comprising 179 pediatric patients who underwent adenotonsillectomy with LMA, Eguia et al. concluded that the use of LMA led to an overall reduced intraoperative time [37].
However, there was a study by Gehrke et al. in which the authors retrospectively analyzed pediatric adenotonsillectomy in around 1500 patients (683 in the LMA group and 849 in the ETT group) [38]. The authors reported that in at least 10 percent of cases, LMA was replaced with ETT and that the complications were more in the LMA group than ETT group. Based on the results of their study, the authors did not support the use of LMA as an airway device for pediatric adenotonsillectomies. The reason why the use of SGA is not used by many anesthesiologists is due to the fear of adverse events and also that the surgeons might find it difficult to operate with the SGA inside. However, the surgeons can be reassured about this, and in case of difficulty, an ETT can always be placed. The results of the meta-analysis also show that the incidence of respiratory adverse events is similar to SGA when compared to ETT.
The strength of this systematic review and meta-analysis is that only RCTs were included in the review. The overall heterogeneity of the studies included was low, but the level of evidence was moderate to low. The limitation was a relatively small number of studies could be analyzed. TSA confirmed that the postoperative recovery time was less with the use of SAD than with ETT. The SADs used were of different types in the included studies. Meta-analysis could be performed for three outcomes only as many outcomes were inconsistently reported.
5. Conclusions
The present systematic review and meta-analysis suggest that when SAD is used for adenotonsillectomy, there is lesser postoperative time and comparable incidence of laryngospasm, but a higher chance of change over to ETT. It is recommended to use SAD for these surgeries by careful selection of patients and also based on the experience of the anesthesiologists and surgeons involved. We suggest the conduction of well-designed and adequate power studies in the future, with a robust methodology to establish the ideal SAD that could be used with a lesser incidence of failure.
Author Contributions
Conceptualization, A.N. and N.B.; methodology, A.N. and S.S.M.; software, A.N.; validation, N.B., U.D. and S.S.M.; formal analysis, A.N.; investigation, A.N. and N.B.; resources, N.B. and U.D.; data curation, A.N.; writing—A.N.; writing—review and editing, N.B.; supervision, N.B.; project administration, U.D. and S.S.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The data used to support the findings of this study are available upon request to the corresponding author.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Bangera, A. Anaesthesia for adenotonsillectomy: An update. Indian J. Anaesth. 2017, 61, 103–109. [Google Scholar] [CrossRef] [Scilit]
- Zalan, J.; Vaccani, J.-P.; Murto, K. Paediatric adenotonsillectomy, part 2: Considerations for anaesthesia. BJA Educ. 2020, 20, 193–200. [Google Scholar] [CrossRef] [Scilit]
- McGuire, S.R.; Doyle, N.M. Update on the safety of anesthesia in young children presenting for adenotonsillectomy. World J. Otorhinolaryngol. Head Neck Surg. 2021, 7, 179–185. [Google Scholar] [CrossRef] [Scilit]
- Kleine-Brueggeney, M.; Gottfried, A.; Nabecker, S.; Greif, R.; Book, M.; Theiler, L. Pediatric supraglottic airway devices in clinical practice: A prospective observational study. BMC Anesthesiol. 2017, 17, 119. [Google Scholar] [CrossRef] [Scilit]
- Huang, A.S.; Hajduk, J.; Jagannathan, N. Advances in supraglottic airway devices for the management of difficult airways in children. Expert. Rev. Med. Devices 2016, 13, 157–169. [Google Scholar] [CrossRef] [Scilit]
- Luce, V.; Harkouk, H.; Brasher, C.; Michelet, D.; Hilly, J.; Maesani, M.; Diallo, T.; Mangalsuren, N.; Nivoche, Y.; Dahmani, S. Supraglottic airway devices vs tracheal intubation in children: A quantitative meta-analysis of respiratory complications. Pediatr. Anesth. 2014, 24, 1088–1098. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gravningsbråten, R.; Nicklasson, B.; Raeder, J. Safety of laryngeal mask airway and short-stay practice in office-based adenotonsillectomy. Acta Anaesthesiol. Scand. 2009, 53, 218–222. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ozmete, O.; Sener, M.; Caliskan, E.; Kipri, M.; Aribogan, A. The use of flexible laryngeal mask airway for Adenoidectomies: An experience of 814 Paediatric patients. Pak. J. Med. Sci. 2017, 33, 823–828. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mandel, J.E. Laryngeal mask airways in ear, nose, and throat procedures. Anesthesiol. Clin. 2010, 28, 469–483. [Google Scholar] [CrossRef] [Scilit]
- Turnbull, J.; Patel, A. The use of the laryngeal mask airway in ENT surgery: Facts and fiction. Trends Anaesth. Crit. Care 2013, 3, 346–350. [Google Scholar] [CrossRef] [Scilit]
- Higgins, J.P.T.; Thomas, J.; Chandler, J.; Cumpston, M.; Li, T.; Page, M.J.; Welch, V.A. (Eds.) Cochrane Handbook for Systematic Reviews of Interventions Version 6.3 (Updated February 2022). Cochrane. 2022. Available online: www.training.cochrane.org/handbook (accessed on 14 January 2024).
- GRADEpro GDT: GRADEpro Guideline Development Tool [Software]. McMaster University, 2015 (Developed by Evidence Prime, Inc.). Available online: https://www.gradepro.org (accessed on 14 January 2024).
- Review Manager (RevMan) [Computer Program]. Version 5.4.; The Cochrane Collaboration. 2020. Available online: http://revman.cochrane.org (accessed on 14 January 2024).
- Sterne, J.A.; Egger, M. Funnel plots for detecting bias in meta-analysis: Guidelines on choice of axis. J. Clin. Epidemiol. 2001, 54, 1046–1055. [Google Scholar] [CrossRef] [Scilit]
- Egger, M.; Smith, G.D.; Schneider, M.; Minder, C. Bias in meta-analysis detected by a simple, graphical test. BMJ 1997, 315, 629–634. [Google Scholar] [CrossRef] [Scilit]
- Kang, H. Trial sequential analysis: Novel approach for meta-analysis. Anesth. Pain. Med. 2021, 16, 138–150. [Google Scholar] [CrossRef] [Scilit]
- De Cassai, A.; Pasin, L.; Boscolo, A.; Salvagno, M.; Navalesi, P. Trial sequential analysis: Plain and simple. Korean J. Anesthesiol. 2021, 74, 363–365. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Doksrød, S.; Løfgren, B.; Nordhammer, A.; Svendsen, M.V.; Gisselsson, L.; Ræder, J. Reinforced laryngeal mask airway compared with endotracheal tube for adenotonsillectomies. Eur. J. Anaesthesiol. 2010, 27, 941–946. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peng, A.; Dodson, K.M.; Thacker, L.R.; Kierce, J.; Shapiro, J.; Baldassari, C.M. Use of laryngeal mask airway in pediatric adenotonsillectomy. Arch. Otolaryngol. Head Neck Surg. 2011, 137, 42–46. [Google Scholar] [CrossRef] [Scilit]
- Ranieri, D., Jr.; Neubauer, A.G.; Ranieri, D.M.; do Nascimento, P., Jr. The use of disposable laryngeal mask airway for adenotonsillectomies. Rev. Bras. Anestesiol. 2012, 62, 788–797. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sierpina, D.I.; Chaudhary, H.; Walner, D.L.; Villines, D.; Schneider, K.; Lowenthal, M.; Aronov, Y. Laryngeal mask airway versus endotracheal tube in pediatric adenotonsillectomy. Laryngoscope 2012, 122, 429–435. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Duran, M.; Kuşderci, H.; Uludağ, Ö. Comparison of flexible laryngeal mask insertion and endotracheal intubation in adenotonsillectomy surgery. Acta Clin. Croat. 2022, 61, 613–619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsu, G.; von Ungern-Sternberg, B.S.; Engelhardt, T. Pediatric airway management. Curr. Opin. Anaesthesiol. 2021, 34, 276–283. [Google Scholar] [CrossRef] [Scilit]
- Harless, J.; Ramaiah, R.; Bhananker, S.M. Pediatric airway management. Int. J. Crit. Illn. Inj. Sci. 2014, 4, 65–70. [Google Scholar] [PubMed]
- Bradley, J.; Lee, G.S.; Peyton, J. Anesthesia for shared airway surgery in children. Pediatr. Anesth. 2020, 30, 288–295. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kundra, P.; Supraja, N.; Agrawal, K.; Ravishankar, M. Flexible laryngeal mask airway for cleft palate surgery in children: A randomized clinical trial on efficacy and safety. Cleft Palate-Craniofacial J. 2009, 46, 368–373. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patel, M.G.; Swadia, V.; Bansal, G. Prospective randomized comparative study of use of PLMA and ET tube for airway management in children under general anaesthesia. Indian J. Anaesth. 2010, 54, 109–115. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, C.-J.; Cheng, P.-L.; Huang, Y.-J.; Huang, F.-H. Laryngeal Mask Airway as an Appropriate Option in Pediatric Laparoscopic Inguinal Hernia Repair: A Systematic Review and Meta-Analysis. J. Pediatr. Surg. 2023. [Google Scholar] [CrossRef] [Scilit]
- Totonchi, Z.; Siamdoust, S.A.S.; Zaman, B.; Rokhtabnak, F.; Alavi, S.A. Comparison of laryngeal mask airway (LMA) insertion with and without muscle relaxant in pediatric anesthesia; a randomized clinical trial. Heliyon 2022, 8, e11504. [Google Scholar] [CrossRef] [Scilit]
- Mir, S.A.; Dhar, R.; Sofi, K.; Jehangir, M.; Wazir, M. Comparison of Spontaneous Ventilation, Pressure Control Ventilation and Pressure Support Ventilation in Pediatric Patients Undergoing Infraumbilical Surgery Using ProSeal Laryngeal Mask Airway. Anesth. Essays Res. 2021, 15, 321–326. [Google Scholar] [CrossRef] [Scilit]
- Wu, L.; Wei, S.W.; Xiang, Z.; Yu, E.Y.; Qu, S.Q.; Du, Z. Effect of neuromuscular block on surgical conditions during short-duration paediatric laparoscopic surgery involving a supraglottic airway. Br. J. Anaesth. 2021, 127, 281–288. [Google Scholar] [CrossRef] [Scilit]
- Lalwani, K.; Richins, S.; Aliason, I.; Milczuk, H.; Fu, R. The laryngeal mask airway for pediatric adenotonsillectomy: Predictors of failure and complications. Int. J. Pediatr. Otorhinolaryngol. 2013, 77, 25–28. [Google Scholar] [CrossRef] [Scilit]
- Aziz, L.; Bashir, K. Comparison of armoured laryngeal mask airway with endotracheal tube for adenotonsillectomy. J. Coll. Physicians Surg. Pak. 2006, 16, 685–688. [Google Scholar]
- Thorning, G.; Robb, P.; Ewah, B.; Shylaja, V. The laryngeal mask airway in elective paediatric day case ENT surgery: A prospective audit. Eur. J. Anaesthesiol. 2016, 33, 872–873. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boroda, N.; Malesinska, M.; Kars, M.S.; Smith, L.P. The use of laryngeal mask airway for adenoidectomy. Int. J. Pediatr. Otorhinolaryngol. 2018, 107, 42–44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ramgolam, A.; Hall, G.; Zhang, G.; Hegarty, M.; von Ungern-Sternberg, B. Deep or awake removal of laryngeal mask airway in children at risk of respiratory adverse events undergoing tonsillectomy—A randomised controlled trial. Br. J. Anaesth. 2018, 120, 571–580. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eguia, A.; Jiang, Z.Y.; Brollier, L.; Matuszczak, M.; Yuksel, S.; Roy, S.; Huang, Z. Reducing intraoperative time with laryngeal mask airway and stretcher in pediatric adenotonsillectomy. Am. J. Otolaryngol. 2022, 43, 103195. [Google Scholar] [CrossRef] [Scilit]
- Gehrke, T.; Hackenberg, S.; Steinhübel, B.; Hagen, R.; Scherzad, A. Laryngeal mask versus intubation for adenoidectomies in children: Analysis of 1500 operations. Laryngoscope 2019, 129, E383–E388. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).