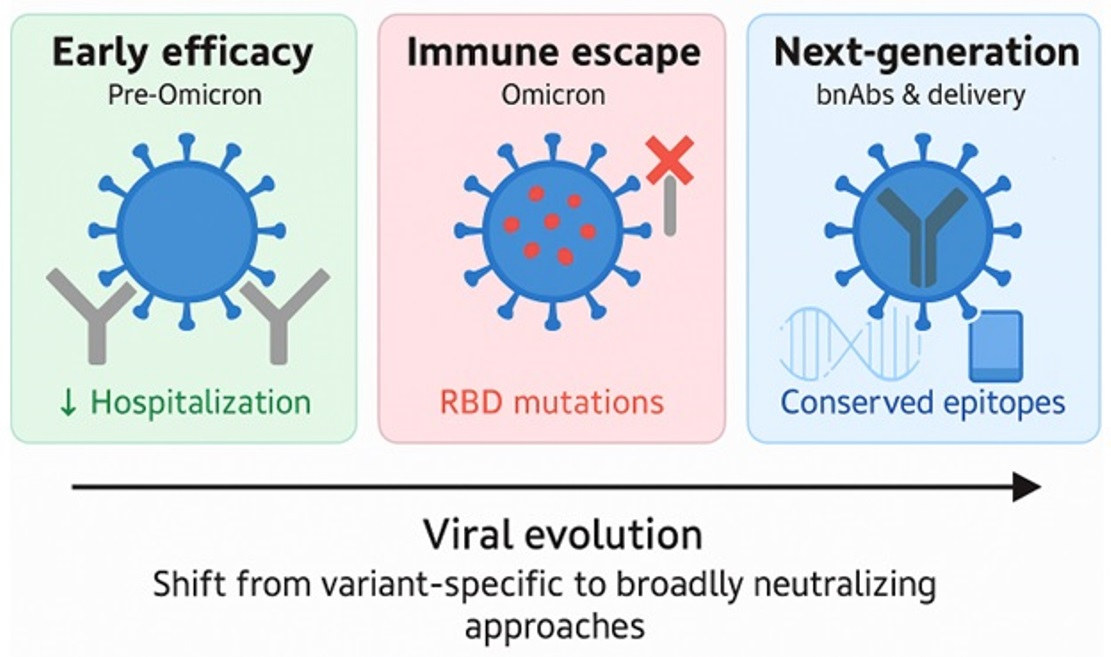
The Shifting Paradigm of Monoclonal Antibodies in COVID-19 Management: From Early Triumphs to Viral Resistance and Future Perspectives



Abstract
1. Introduction
2. Viral Pathogenesis, Immune Evasion, and Therapeutic Targets
2.1. First-Generation Neutralizing mAbs: The Era of Clinical Efficacy
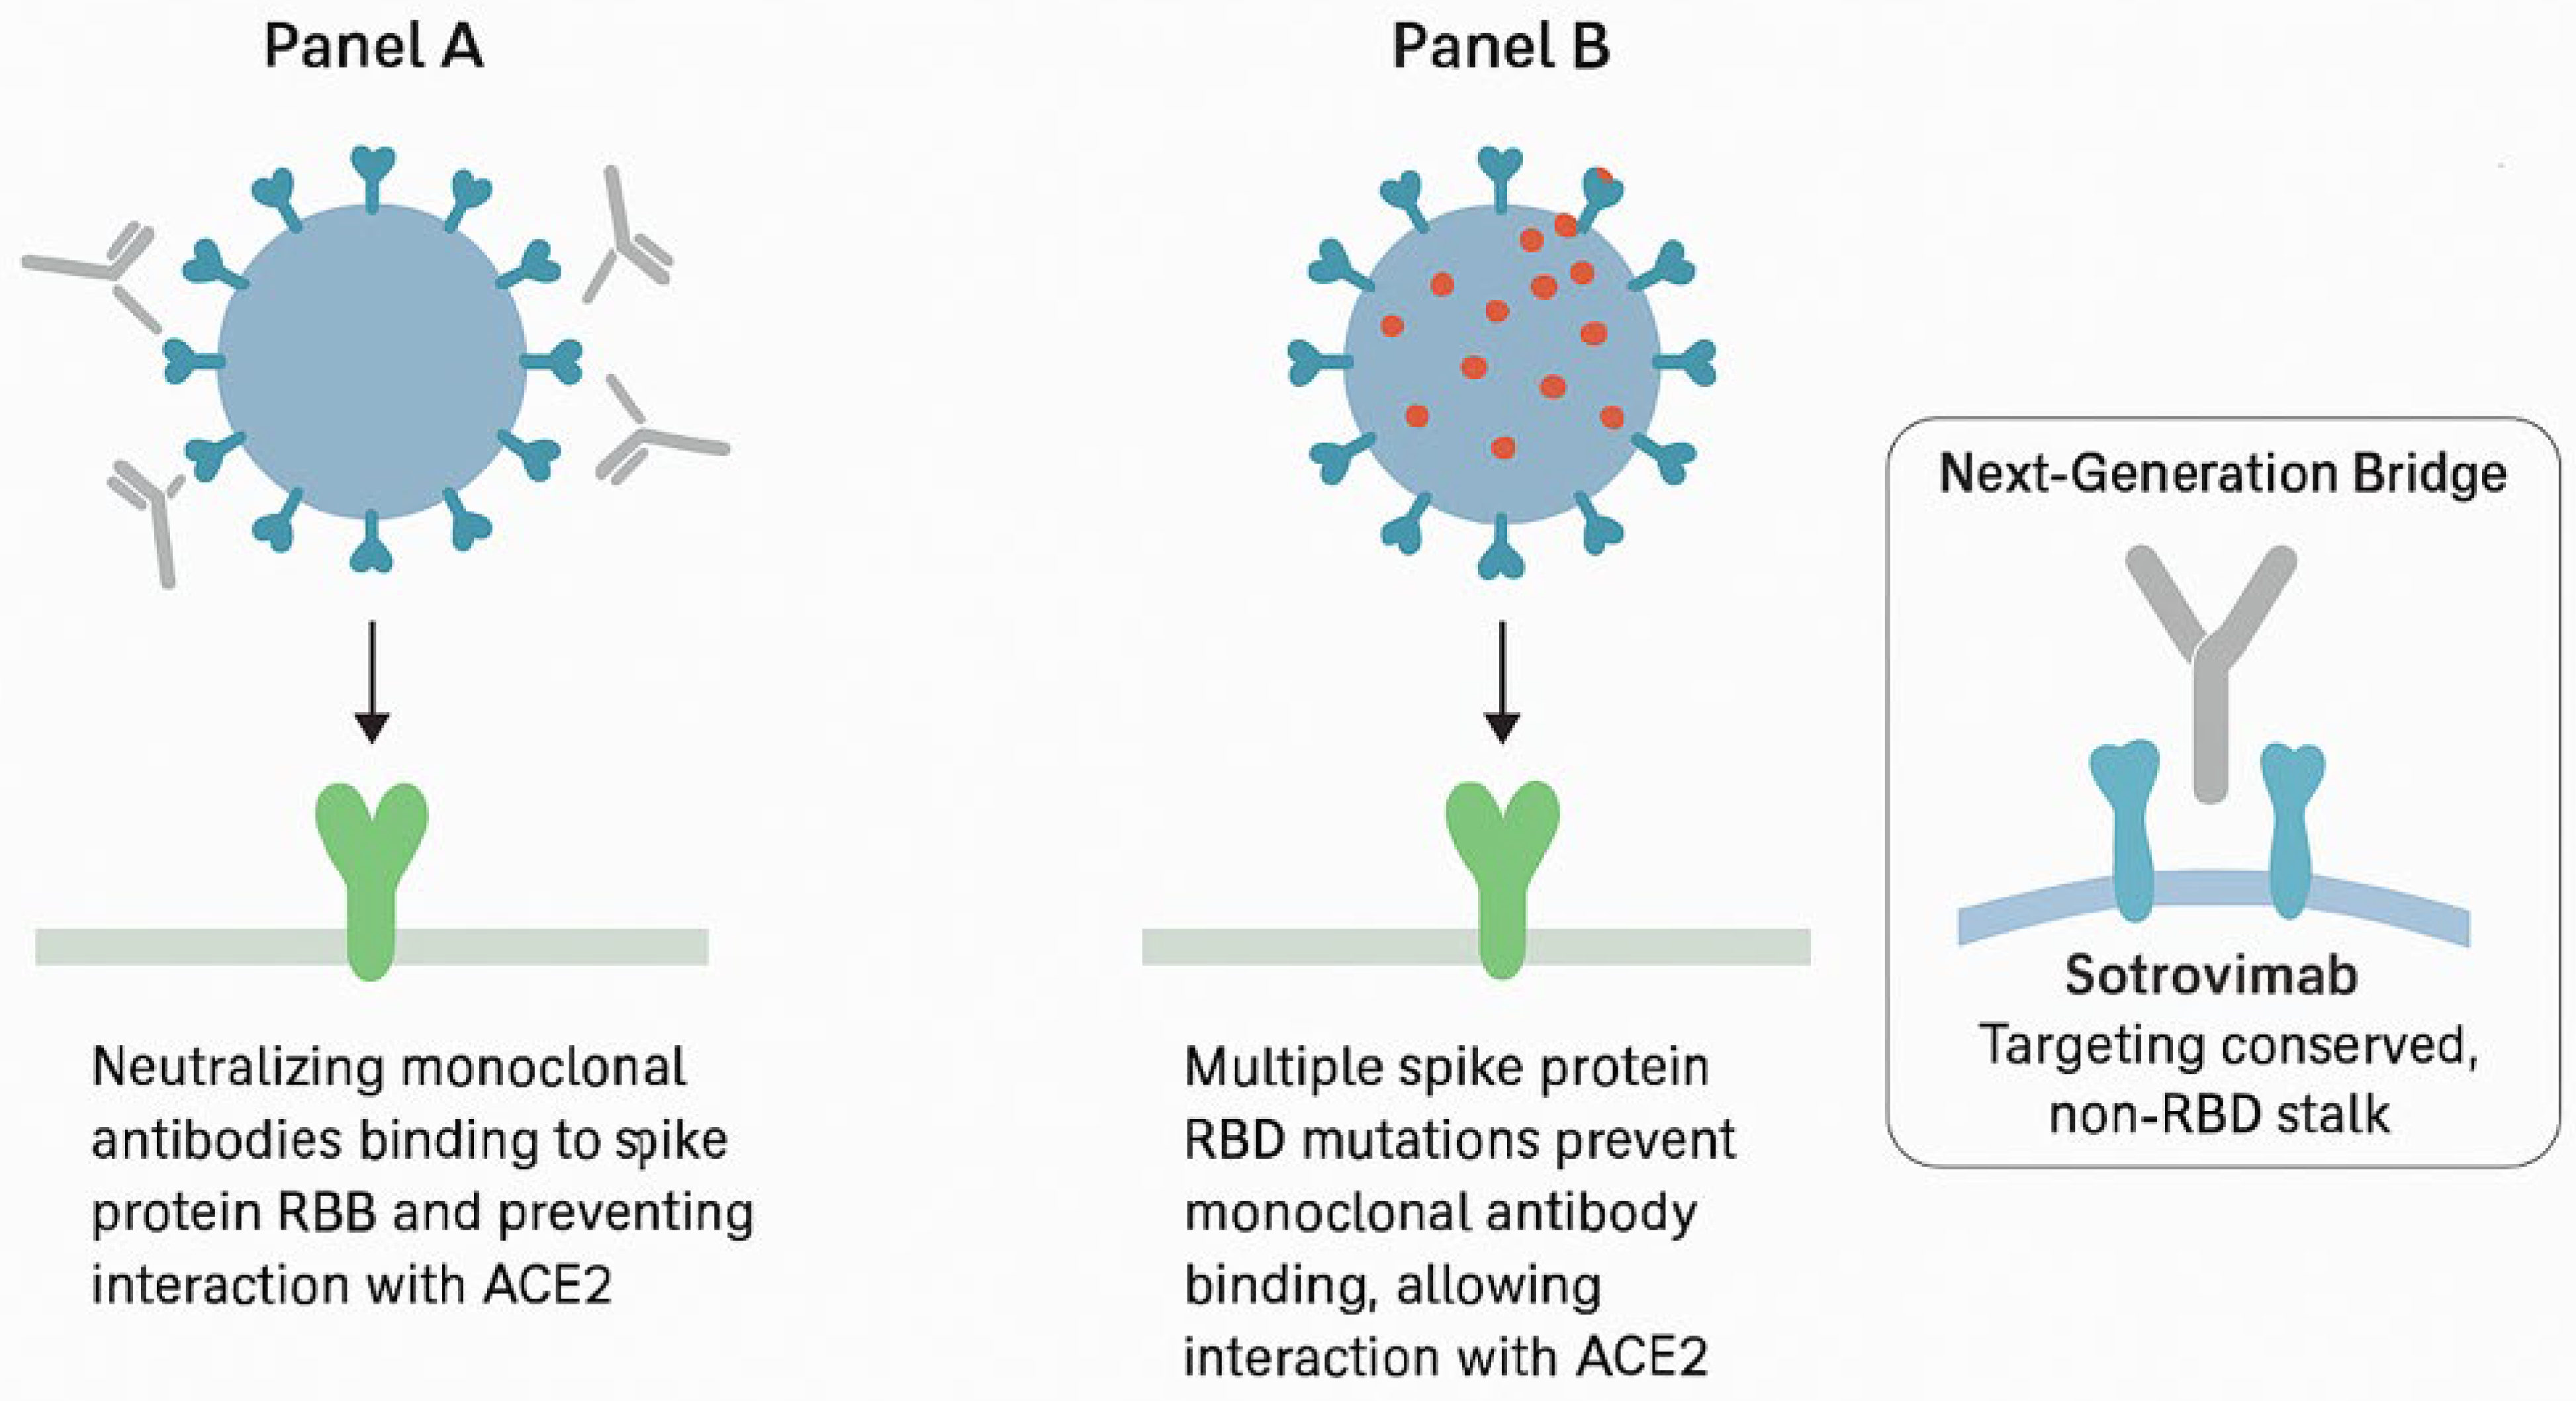
2.2. Later-Generation mAbs: Sotrovimab, Bebtelovimab, and the Evolutionary Arms Race
3. Long COVID and Systemic Complications
4. The Role of Clinical Pharmacy, Antimicrobial Stewardship, and Healthcare Sustainability
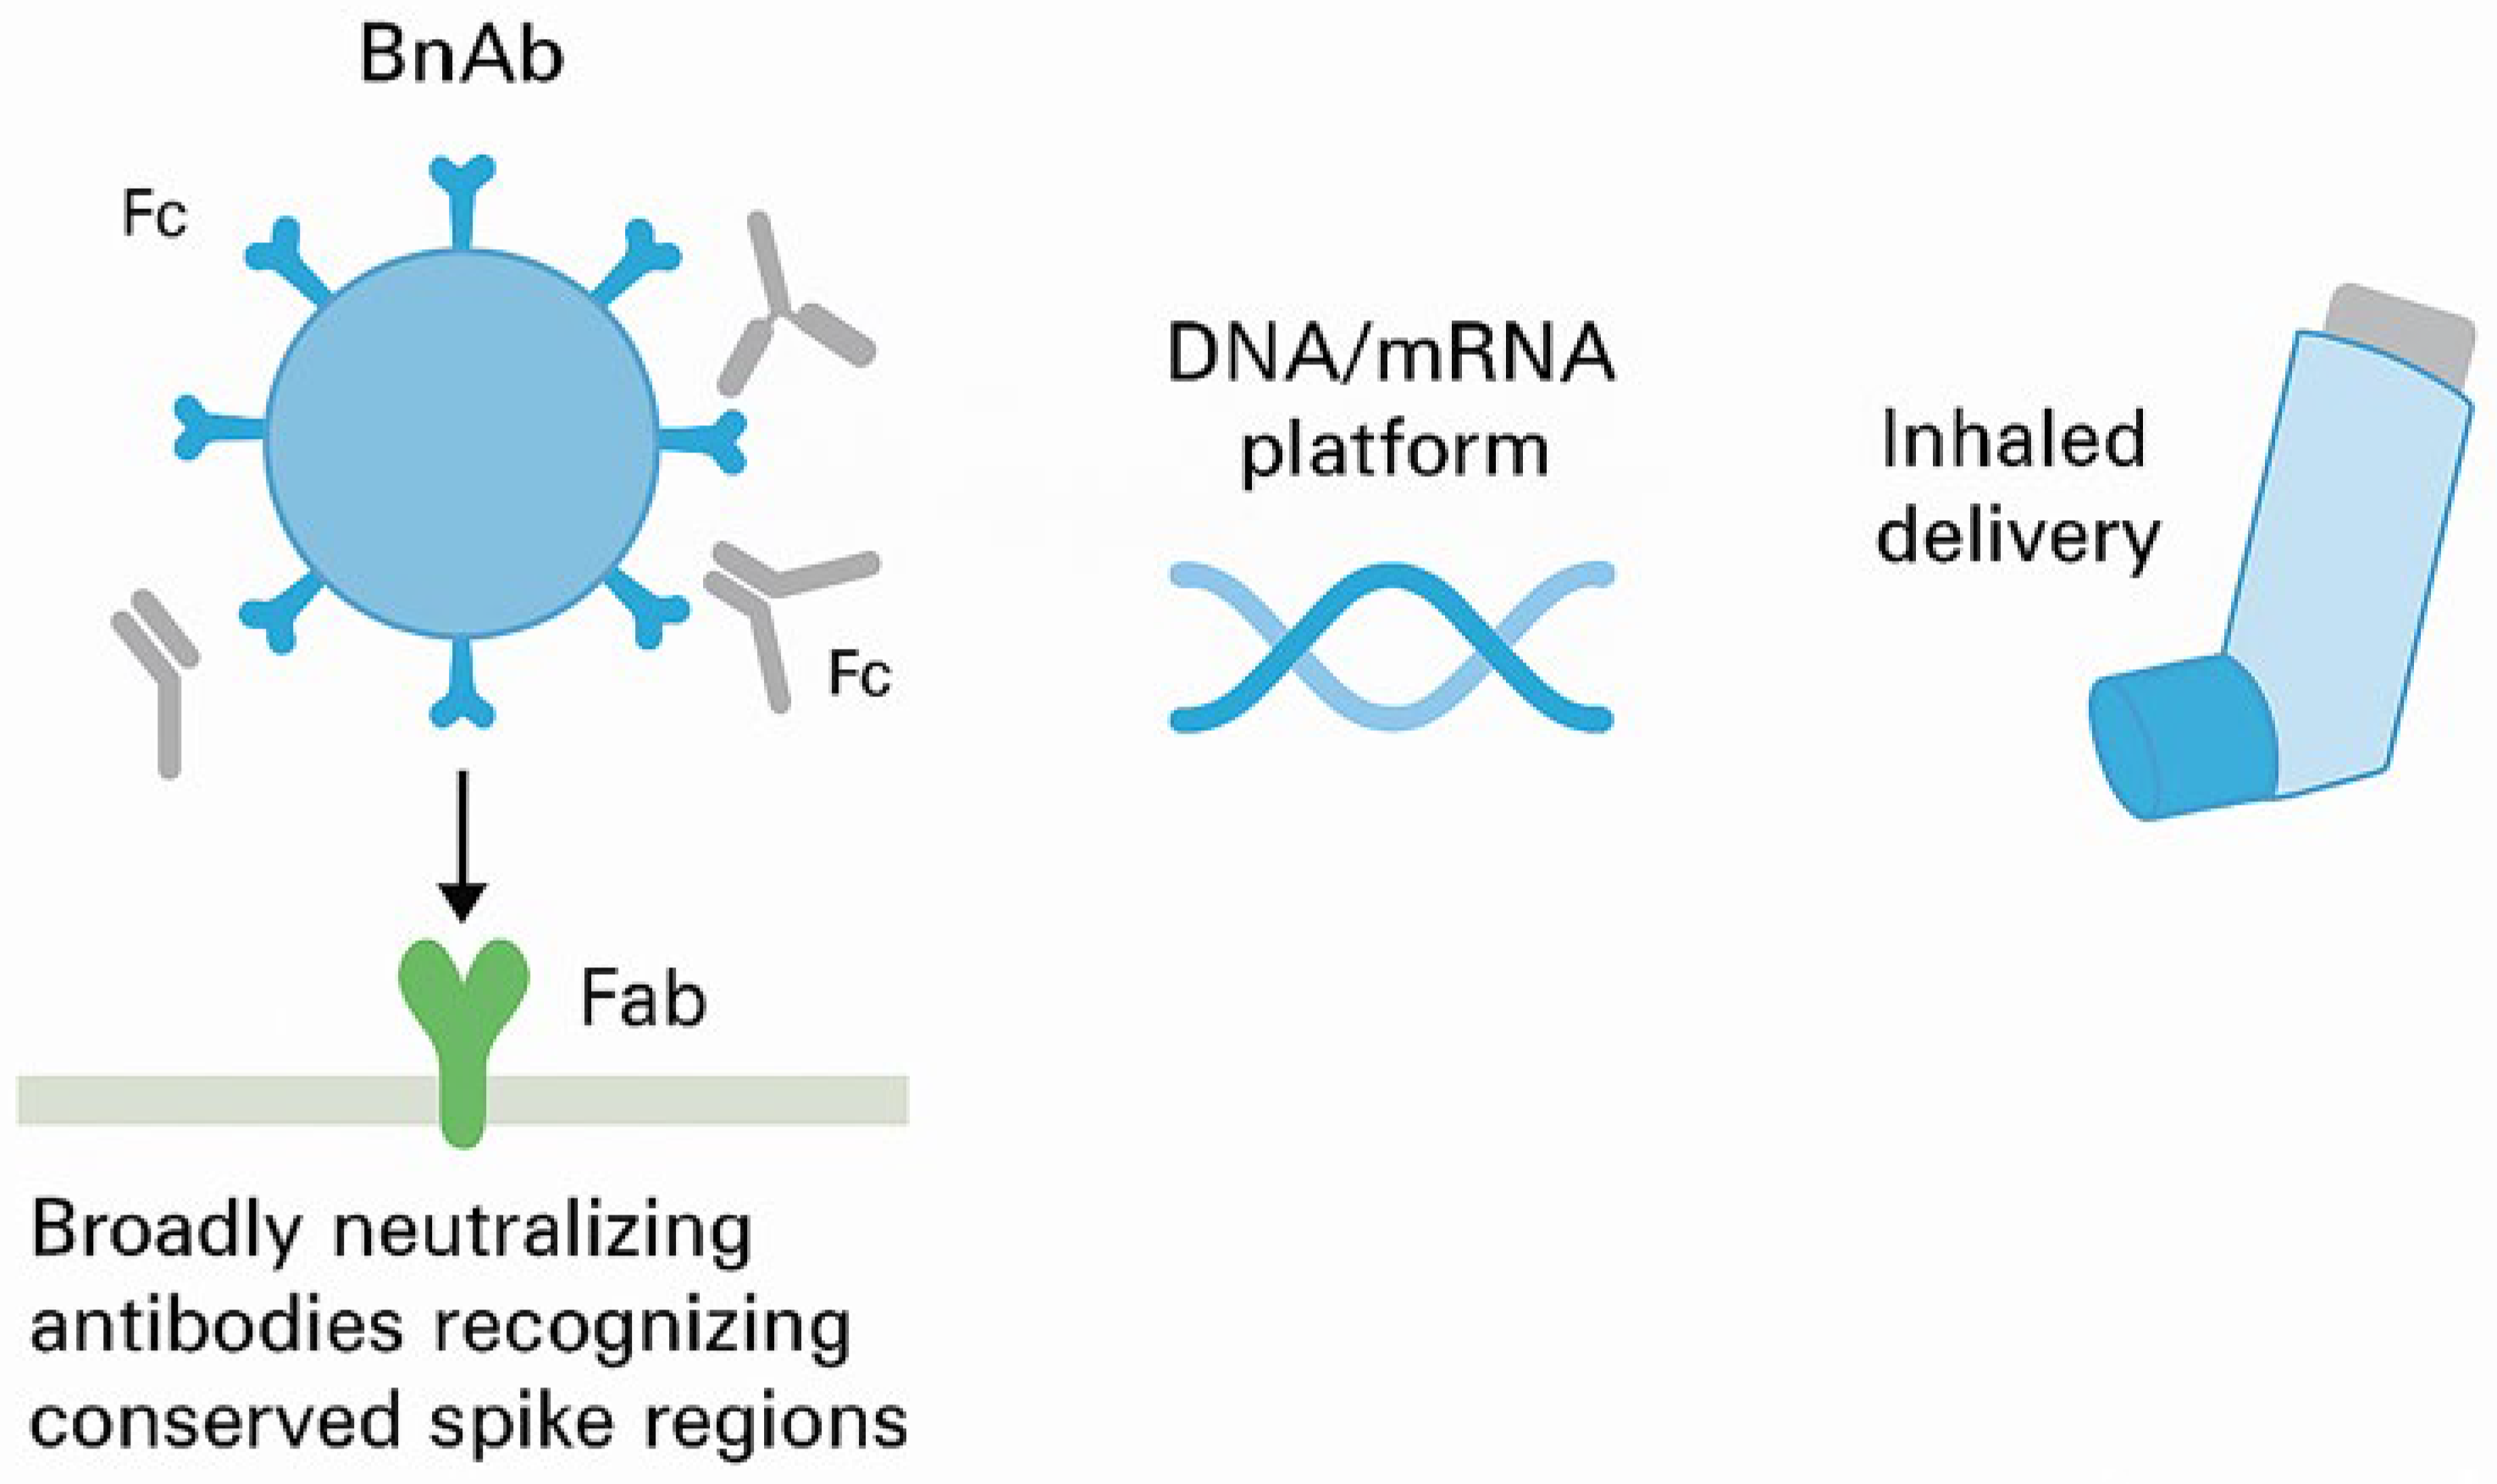
5. Future Directions and Next-Generation Antibody Therapeutics
6. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
Abbreviations
| ACE2 | Angiotensin-Converting Enzyme 2 |
| ADCC | Antibody-Dependent Cellular Cytotoxicity |
| ADCP | Antibody-Dependent Cellular Phagocytosis |
| AIFA | Italian Medicines Agency (Agenzia Italiana del Farmaco) |
| ARDS | Acute Respiratory Distress Syndrome |
| bnAbs | Broadly Neutralizing Antibodies |
| CDC | Complement-Dependent Cytotoxicity |
| CGRP | Calcitonin Gene-Related Peptide |
| COVID-19 | Coronavirus Disease 2019 |
| CRP | C-Reactive Protein |
| dMAbs | DNA-Encoded Monoclonal Antibodies |
| DNA | Deoxyribonucleic Acid |
| EMA | European Medicines Agency |
| Fc | Fragment Crystallizable |
| FcγRs | Fc Gamma Receptors |
| FDA | Food and Drug Administration |
| ICU | Intensive Care Unit |
| IgG1 | Immunoglobulin G Subclass 1 |
| IL-1b | Interleukin-1 Beta |
| IL-6 | Interleukin-6 |
| LNP | Lipid Nanoparticle |
| mAbs | Monoclonal Antibodies |
| MALT | Mucosal-Associated Lymphoid Tissue |
| ME/CFS | Myalgic Encephalomyelitis/Chronic Fatigue Syndrome |
| mRNA | Messenger Ribonucleic Acid |
| PASC | Post-Acute Sequelae of SARS-CoV-2 infection |
| POTS | Postural Orthostatic Tachycardia Syndrome |
| RBD | Receptor-Binding Domain |
| RNA | Ribonucleic Acid |
| S protein | Spike Protein |
| SARS-CoV-2 | Severe Acute Respiratory Syndrome Coronavirus 2 |
| TMPRSS2 | Transmembrane Serine Protease 2 |
| TNF-a | Tumor Necrosis Factor-alpha |
| VOCs | Variants of Concern |
References
- Zhu, N.; Zhang, D.; Wang, W.; Li, X.; Yang, B.; Song, J.; Zhao, X.; Huang, B.; Shi, W.; Lu, R.; et al. A Novel Coronavirus from Patients with Pneumonia in China, 2019. N. Engl. J. Med. 2020, 382, 727–733. [Google Scholar] [CrossRef] [Scilit]
- Wiersinga, W.J.; Rhodes, A.; Cheng, A.C.; Peacock, S.J.; Prescott, H.C. Pathophysiology, Transmission, Diagnosis, and Treatment of Coronavirus Disease 2019 (COVID-19): A Review. JAMA 2020, 324, 782–793. [Google Scholar] [CrossRef] [Scilit]
- Beigel, J.H.; Tomashek, K.M.; Dodd, L.E.; Mehta, A.K.; Zingman, B.S.; Kalil, A.C.; Hohmann, E.; Chu, H.Y.; Luetkemeyer, A.; Kline, S.; et al. Remdesivir for the Treatment of Covid-19—Final Report. N. Engl. J. Med. 2020, 383, 1813–1826. [Google Scholar] [CrossRef] [Scilit]
- Taylor, P.C.; Adams, A.C.; Hufford, M.M.; de la Torre, I.; Winthrop, K.; Gottlieb, R.L. Neutralizing monoclonal antibodies for treatment of COVID-19. Nat. Rev. Immunol. 2021, 21, 382–393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Corti, D.; Purcell, L.A.; Snell, G.; Veesler, D. Tackling COVID-19 with neutralizing monoclonal antibodies. Cell 2021, 184, 3086–3108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vitiello, A.; Porta, R.; Pianesi, L.; Ferrara, F. COVID-19 pandemic: Vaccine and new monoclonal antibodies, point of view. Ir. J. Med. Sci. 2022, 191, 483–484. [Google Scholar] [CrossRef] [Scilit]
- Harvey, W.T.; Carabelli, A.M.; Jackson, B.; Gupta, R.K.; Thomson, E.C.; Harrison, E.M.; Ludden, C.; Reeve, R.; Rambaut, A. SARS-CoV-2 variants, spike mutations and immune escape. Nat. Rev. Microbiol. 2021, 19, 409–424. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Coronaviridae Study Group of the International Committee on Taxonomy of Viruses. The species Severe acute respiratory syndrome-related coronavirus: Classifying 2019-nCoV and naming it SARS-CoV-2. Nat. Microbiol. 2020, 5, 536–544. [Google Scholar] [CrossRef] [Scilit]
- Lan, J.; Ge, J.; Yu, J.; Shan, S.; Zhou, H.; Fan, S.; Zhang, Q.; Shi, X.; Wang, Q.; Zhang, L.; et al. Structure of the SARS-CoV-2 spike receptor-binding domain bound to the ACE2 receptor. Nature 2020, 581, 215–220. [Google Scholar] [CrossRef] [Scilit]
- Walls, A.C.; Park, Y.J.; Tortorici, M.A.; Wall, A.; McGuire, A.T.; Veesler, D. Structure, Function, and Antigenicity of the SARS-CoV-2 Spike Glycoprotein. Cell 2020, 181, 281–292.e6. [Google Scholar] [CrossRef] [Scilit]
- Hoffmann, M.; Kleine-Weber, H.; Schroeder, S.; Krüger, N.; Herrler, T.; Erichsen, S.; Schiergens, T.S.; Herrler, G.; Wu, N.H.; Nitsche, A.; et al. SARS-CoV-2 Cell Entry Depends on ACE2 and TMPRSS2 and Is Blocked by a Clinically Proven Protease Inhibitor. Cell 2020, 181, 271–280.e8. [Google Scholar] [CrossRef] [Scilit]
- Shang, J.; Wan, Y.; Luo, C.; Ye, G.; Geng, Q.; Auerbach, A.; Li, F. Cell entry mechanisms of SARS-CoV-2. Proc. Natl. Acad. Sci. USA 2020, 117, 11727–11734. [Google Scholar] [CrossRef] [Scilit]
- Barnes, C.O.; Jette, C.A.; Abernathy, M.E.; Dam, K.A.; Esswein, S.R.; Gristick, H.B.; Malyutin, A.G.; Sharaf, N.G.; Huey-Tubman, K.E.; Lee, Y.E.; et al. SARS-CoV-2 neutralizing antibody structures inform therapeutic strategies. Nature 2020, 588, 682–687. [Google Scholar] [CrossRef] [Scilit]
- Winkler, E.S.; Gilchuk, P.; Yu, J.; Bailey, A.L.; Chen, R.E.; Chong, Z.; Zost, S.J.; Jang, H.; Huang, Y.; Allen, J.D.; et al. Human neutralizing antibodies against SARS-CoV-2 require intact Fc effector functions for optimal therapeutic protection. Cell 2021, 184, 1804–1820.e16. [Google Scholar] [CrossRef] [Scilit]
- Merad, M.; Martin, J.C. Pathological inflammation in patients with COVID-19: A key role for monocytes and macrophages. Nat. Rev. Immunol. 2020, 20, 355–362. [Google Scholar] [CrossRef] [Scilit]
- Fajgenbaum, D.C.; June, C.H. Cytokine Storm. N. Engl. J. Med. 2020, 383, 2255–2273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ackermann, M.; Verleden, S.E.; Kuehnel, M.; Haverich, A.; Welte, T.; Laenger, F.; Vanstapel, A.; Werlein, C.; Stark, H.; Tzankov, A.; et al. Pulmonary Vascular Endothelialitis, Thrombosis, and Angiogenesis in Covid-19. N. Engl. J. Med. 2020, 383, 120–128. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gandhi, R.T.; Lynch, J.B.; Del Rio, C. Mild or Moderate Covid-19. N. Engl. J. Med. 2020, 383, 1757–1766. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cohen, M.S. Monoclonal Antibodies to Disrupt Progression of Early Covid-19 Infection. N. Engl. J. Med. 2021, 384, 958–959. [Google Scholar] [CrossRef] [Scilit]
- Jones, C.E.; Magarian, A.L.; Knorr, H.A. Clinical efficacy of bamlanivimab. JAMA 2021, 325, 632–644. [Google Scholar]
- Gottlieb, R.L.; Nirula, A.; Chen, P.; Boscia, J.; Heller, B.; Morris, J.; Huhn, G.; Cardona, J.; Mocherla, B.; Stosor, V. Effect of Bamlanivimab as Monotherapy or in Combination with Etesevimab on Viral Load in Patients with Mild to Moderate COVID-19. JAMA 2021, 325, 632–644. [Google Scholar] [CrossRef] [Scilit]
- Shokri, A. Efficacy and safety of bamlanivimab in patients with COVID-19: A systematic review and meta-analysis. World J. Virol. 2024, 13, 88660. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dougan, M.; Nirula, A.; Azizad, M.; Mocherla, B.; Gottlieb, R.L.; Chen, P.; Hebert, C.; Perry, R.; Boscia, J.; Heller, B.; et al. Bamlanivimab plus Etesevimab in Mild or Moderate Covid-19. N. Engl. J. Med. 2021, 385, 1382–1392. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baum, A.; Fulton, B.O.; Wloga, E.; Copin, R.; Pascal, K.E.; Russo, V.; Giordano, S.; Lanza, K.; Negron, N.; Ni, M.; et al. Antibody cocktail to SARS-CoV-2 spike protein prevents rapid mutational escape seen with individual antibodies. Science 2020, 369, 1014–1018. [Google Scholar] [CrossRef] [Scilit]
- Hansen, J.; Baum, A.; Pascal, K.E.; Russo, V.; Giordano, S.; Wloga, E.; Fulton, B.O.; Yan, Y.; Koon, K.; Patel, K.; et al. Studies in humanized mice and convalescent humans yield a SARS-CoV-2 antibody cocktail. Science 2020, 369, 1010–1014. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- RECOVERY Collaborative Group. Casirivimab and imdevimab in patients admitted to hospital with COVID-19 (RECOVERY): A randomised, controlled, open-label, platform trial. Lancet 2022, 399, 665–676. [Google Scholar] [CrossRef] [Scilit]
- Weinreich, D.M.; Sivapalasingam, S.; Norton, T.; Ali, S.; Gao, H.; Bhore, R.; Xiao, J.; Hooper, A.T.; Hamilton, J.D.; Musser, B.J.; et al. REGEN-COV Antibody Combination and Outcomes in Outpatients with Covid-19. N. Engl. J. Med. 2021, 385, e81. [Google Scholar] [CrossRef] [Scilit]
- Streinu-Cercel, A.; Săndulescu, O.; Preotescu, L.L.; Kim, J.Y.; Kim, Y.S.; Cheon, S.; Jang, Y.R.; Lee, S.J.; Kim, S.H.; Chang, I.; et al. Efficacy and Safety of Regdanvimab (CT-P59): A Phase 2/3 Randomized, Double-Blind, Placebo-Controlled Trial in Outpatients with Mild-to-Moderate Coronavirus Disease 2019. Open Forum Infect. Dis. 2022, 9, ofac053. [Google Scholar] [CrossRef] [Scilit]
- Kim, J.Y.; Săndulescu, O.; Preotescu, L.L.; Rivera-Martínez, N.E.; Dobryanska, M.; Birlutiu, V.; Miftode, E.G.; Gaibu, N.; Caliman-Sturdza, O.; Florescu, S.A.; et al. A Randomized Clinical Trial of Regdanvimab in High-Risk Patients with Mild-to-Moderate Coronavirus Disease 2019. Open Forum Infect. Dis. 2022, 9, ofac406. [Google Scholar] [CrossRef] [Scilit]
- Robbie, G.J.; Criste, R.; Dall’acqua, W.F.; Jensen, K.; Patel, N.K.; Losonsky, G.A.; Griffin, M.P. A novel investigational Fc-modified humanized monoclonal antibody, motavizumab-YTE, has an extended half-life in healthy adults. Antimicrob. Agents Chemother. 2013, 57, 6147–6153. [Google Scholar] [CrossRef] [Scilit]
- Loo, Y.M.; McTamney, P.M.; Arends, R.H.; Abram, M.E.; Aksyuk, A.A.; Diallo, S.; Flores, D.J.; Kelly, E.J.; Ren, K.; Roque, R.; et al. The SARS-CoV-2 monoclonal antibody combination, AZD7442, is protective in nonhuman primates and has an extended half-life in humans. Sci. Transl. Med. 2022, 14, eabl8124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Le, R.Q.; Li, L.; Yuan, W.; Shord, S.S.; Nie, L.; Habtemariam, B.A.; Przepiorka, D.; Farrell, A.T.; Pazdur, R. FDA Approval Summary: Tocilizumab for Treatment of Chimeric Antigen Receptor T Cell-Induced Severe Cytokine Release Syndrome. Oncologist 2018, 23, 943–947. [Google Scholar] [CrossRef] [Scilit]
- Stone, J.H.; Frigault, M.J.; Serling-Boyd, N.J.; Fernandes, A.D.; Harvey, L.; Foulkes, A.S.; Horick, N.K.; Healy, B.C.; Shah, R.; Bensaci, A.M. Efficacy of Tocilizumab in Patients Hospitalized with Covid-19. N. Engl. J. Med. 2020, 383, 2333–2344. [Google Scholar] [CrossRef] [Scilit]
- RECOVERY Collaborative Group. Tocilizumab in patients admitted to hospital with COVID-19 (RECOVERY): A randomised, controlled, open-label, platform trial. Lancet 2021, 397, 1637–1645. [Google Scholar] [CrossRef] [Scilit]
- REMAP-CAP Investigators. Interleukin-6 Receptor Antagonists in Critically Ill Patients with Covid-19. N. Engl. J. Med. 2021, 384, 1491–1502. [Google Scholar] [CrossRef] [Scilit]
- Lescure, F.X.; Honda, H.; Fowler, R.A.; Lazar, J.S.; Shi, G.; Wung, P.; Patel, N.; Hagino, O. Sarilumab in patients admitted to hospital with severe or critical COVID-19: A randomised, double-blind, placebo-controlled, phase 3 trial. Lancet Respir. Med. 2021, 9, 522–532. [Google Scholar] [CrossRef] [Scilit]
- Vitiello, A.; La Porta, R.; Trama, U.; Ferrara, F.; Zovi, A.; Auti, A.M.; Di Domenico, M.; Boccellino, M. Pandemic COVID-19, an update of current status and new therapeutic strategies. Naunyn Schmiedebergs Arch. Pharmacol. 2022, 395, 393–398. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Viana, R.; Moyo, S.; Amoako, D.G.; Tegally, H.; Scheepers, C.; Althaus, C.L.; Anyaneji, U.J.; Bester, P.A.; Boni, M.F.; Chand, M.; et al. Rapid epidemic expansion of the SARS-CoV-2 Omicron variant in southern Africa. Nature 2022, 603, 679–686. [Google Scholar] [CrossRef]
- McCallum, M.; Czudnochowski, N.; Rosen, L.E.; Zepeda, S.K.; Bowen, J.E.; Walls, A.C.; Hauser, K.; Joshi, A.; Stewart, C.; Dillen, J.R.; et al. Structural basis of SARS-CoV-2 Omicron immune evasion and receptor engagement. Science 2022, 375, 864–868. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cao, Y.; Wang, J.; Jian, F.; Xiao, T.; Song, W.; Yisimayi, A.; Huang, W.; Li, Q.; Wang, P.; An, R.; et al. Omicron escapes the majority of existing SARS-CoV-2 neutralizing antibodies. Nature 2022, 602, 657–663. [Google Scholar] [CrossRef]
- VanBlargan, L.A.; Errico, J.M.; Halfmann, P.J. An infectious SARS-CoV-2 B.1.1.529 Omicron virus escapes neutralization by therapeutic monoclonal antibodies. Nat. Med. 2022, 28, 490–495. [Google Scholar] [CrossRef] [Scilit]
- Cameroni, E.; Bowen, J.E.; Rosen, L.E.; Saliba, C.; Zepeda, S.K.; Culap, K.; Pinto, D.; VanBlargan, L.A.; De Marco, A.; di Iulio, J.; et al. Broadly neutralizing antibodies overcome SARS-CoV-2 Omicron antigenic shift. Nature 2022, 602, 664–670. [Google Scholar] [CrossRef] [Scilit]
- Cox, R.M. SARS-CoV-2 resistance to monoclonal antibodies and small-molecule drugs. Antivir. Res. 2024, 222, 105804. [Google Scholar]
- Pinto, D.; Park, Y.J.; Beltramello, M.; Walls, A.C.; Tortorici, M.A.; Bianchi, S.; Jaconi, S.; Culap, K.; Zatta, F.; De Marco, A.; et al. Cross-neutralization of SARS-CoV-2 by a human monoclonal SARS-CoV antibody. Nature 2020, 583, 290–295. [Google Scholar] [CrossRef] [Scilit]
- Vitiello, A.; Ferrara, F.; Auti, A.M.; Di Domenico, M.; Boccellino, M. Advances in the Omicron variant development. J. Intern. Med. 2022, 292, 81–90. [Google Scholar] [CrossRef] [Scilit]
- Dejnirattisai, W.; Huo, J.; Zhou, D. SARS-CoV-2 Omicron-B.1.1.529 leads to widespread escape from neutralizing antibody responses. Cell 2022, 185, 467–484.e15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gupta, A.; Gonzalez-Rojas, Y.; Juarez, E.; Crespo Casal, M.; Moya, J.; Falci, D.R.; Sarkis, E.; Solis, J.; Zheng, H.; Scott, N.; et al. Early Treatment for Covid-19 with SARS-CoV-2 Neutralizing Antibody Sotrovimab. N. Engl. J. Med. 2021, 385, 1941–1950. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iketani, S.; Liu, L.; Guo, Y.; Liu, L.; Chan, J.F.; Huang, Y.; Wang, M.; Luo, Y.; Yu, J.; Chu, H.; et al. Antibody evasion properties of SARS-CoV-2 Omicron sublineages. Nature 2022, 604, 553–556. [Google Scholar] [CrossRef] [Scilit]
- Russo, A.; Grimaldi, P.; Pisaturo, M.; Onorato, L.; Coppola, N. Efficacy of sotrovimab on omicron BA.2, BA.4 and BA.5 subvariants of SARS-CoV-2 vs. other early therapies: A systematic review and meta-analysis of literature data. Front. Immunol. 2024, 15, 1295029. [Google Scholar] [CrossRef] [Scilit]
- Westendorf, K.; Žentelis, S.; Wang, L.; Foster, D.; Vaillancourt, P.; Wiggin, M.; Lovett, E.; van der Lee, R.; Hendle, J.; Pustilnik, A. Bebtelovimab, a potent anti-SARS-CoV-2 neutralizing monoclonal antibody, targets a highly conserved epitope. Mol. Cell 2022, 82, 2434–2443.e5. [Google Scholar]
- Wang, Q.; Iketani, S.; Li, Z.; Liu, L.; Guo, Y.; Huang, Y.; Bowen, A.D.; Liu, M.; Wang, M.; Yu, J. Alarming antibody evasion properties of rising SARS-CoV-2 BQ and XBB subvariants. Cell 2023, 186, 279–286.e8. [Google Scholar] [CrossRef] [Scilit]
- Al-Aly, Z.; Bowe, B.; Xie, Y. Long COVID after breakthrough SARS-CoV-2 infection. Nat. Med. 2022, 28, 1461–1467. [Google Scholar] [CrossRef] [Scilit]
- Davis, H.E.; McCorkell, L.; Vogel, J.M.; Topol, E.J. Long COVID: Major findings, mechanisms and recommendations. Nat. Rev. Microbiol. 2023, 21, 133–146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Proal, A.D.; VanElzakker, M.B. Long COVID or Post-acute Sequelae of COVID-19 (PASC): An Overview of Biological Factors That May Contribute to Persistent Symptoms. Front. Microbiol. 2021, 12, 698169. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xie, Y.; Choi, T.; Al-Aly, Z. Nirmatrelvir and the Risk of Post-Acute Sequelae of COVID-19. JAMA Intern. Med. 2023, 183, 554–564. [Google Scholar] [CrossRef] [Scilit]
- Ferrara, F.; Zovi, A.; Masi, M.; Langella, R.; Trama, U.; Boccellino, M.; Vitiello, A. Long COVID could become a widespread post-pandemic disease? A debate on the organs most affected. Naunyn Schmiedebergs Arch. Pharmacol. 2023, 396, 1583–1589. [Google Scholar] [CrossRef] [Scilit]
- Ferrara, F.; Zovi, A.; Giua-Marassi, C. The key role of clinical pharmacists in medication safety strategies. G. Ital. Farm. Clin. 2023, 37, 179–185. [Google Scholar]
- Ferrara, F.; Zovi, A.; Nava, E.; Trama, U.; Sorrentino, S.; Vitiello, A. Il contrasto dell’antibiotico-resistenza: Serve una nuova linea di azione. Recenti Progress. Med. 2022, 113, 588–592. [Google Scholar] [CrossRef] [Scilit]
- Zovi, A.; Vitiello, A.; Langella, R.; Lasala, R.; Ferrara, F. Anticorpi monoclonali anti-CGRP per il trattamento preventivo degli attacchi di emicrania: Un’analisi costo-efficacia nello scenario italiano. Recenti Progress. Med. 2023, 114, 28–35. [Google Scholar] [CrossRef] [Scilit]
- Ferrara, F.; Trama, U.; Nava, E.; Langella, R.; Valentino, F.; Zovi, A. Distress psicologico durante la pandemia da Covid-19: Un’analisi sull’uso di farmaci antipsicotici in un campione di popolazione italiana. Riv. Psichiatr. 2023, 58, 220–225. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Langford, B.J.; So, M.; Raybardhan, S.; Leung, V.; Westwood, D.; MacFadden, D.R.; Soucy, J.R.; Daneman, N. Bacterial co-infection and secondary infection in patients with COVID-19: A living rapid review and meta-analysis. Clin. Microbiol. Infect. 2020, 26, 1622–1629. [Google Scholar] [CrossRef] [Scilit]
- Ferrara, F.; Zovi, A.; Nava, E.; Trama, U.; Vitiello, A. SARS-CoV-2 caused a surge in antibiotic consumption causing a silent pandemic inside the pandemic. A retrospective analysis of Italian data in the first half of 2022. Ann. Pharm. Françaises 2023, 81, 627–635. [Google Scholar] [CrossRef] [Scilit]
- Ferrara, F.; Zovi, A.; Nava, E.; Langella, R.; Vitiello, A. Great sustainability results from appropriate pharmacological therapy. Curr. Probl. Cardiol. 2023, 48, 101857. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hotez, P.J.; Bottazzi, M.E.; Corry, D.B. The tragedy of the anti-vaccine movement and COVID-19. Microbes Infect. 2021, 23, 104886. [Google Scholar]
- Park, Y.J.; Pinto, D.; Walls, A.C.; Liu, Z.; De Marco, A.; Benigni, F.; Zatta, F.; Silacci-Fregni, C.; Bassi, J.; Sprouse, K.R.; et al. Imprinting of antibody responses against SARS-CoV-2. Science 2022, 375, 868–874. [Google Scholar]
- Tebas, P.; Patel, A.; Agnes, J.T.; Parzych, E.M.; Baer, A.; Caturla, M.; Ghosh, S.; Purwar, M.; Bedanova, N.; Tsang, C.; et al. Safety and pharmacokinetics of SARS-CoV-2 DNA-encoded monoclonal antibodies in healthy adults: A phase 1 trial. Nat. Med. 2025, 31, 4150–4159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Piepenbrink, M.S.; Park, J.G.; Oladunni, F.S.; Deshpande, A.; Basu, M.; Sarkar, S.; Loos, A.; Woo, J.; Lovalenti, P.; Sloan, D.; et al. Therapeutic activity of an inhaled potent SARS-CoV-2 neutralizing human monoclonal antibody in hamsters. Cell Rep. Med. 2021, 2, 100218. [Google Scholar] [CrossRef] [Scilit]



| Monoclonal Antibody | Category/Generation | Target/Mechanism of Action | Reference Clinical Trials | Efficacy and Impact of Variants (Especially Omicron) |
|---|---|---|---|---|
| Bamlanivimab (monotherapy) | Neutralizing (First Generation) | Binds an RBD epitope overlapping the ACE2 binding site. | Early clinical studies/initial authorization experience. | Monotherapy was associated with emergence of resistant escape variants; single-agent use was discontinued. |
| Bamlanivimab + Etesevimab | Neutralizing cocktail (First Generation) | Two antibodies binding distinct, non-overlapping RBD epitopes. | BLAZE-1 (reduced hospitalization/death in high-risk outpatients). | Active against Alpha/Delta; markedly reduced neutralization with Omicron, limiting clinical utility. |
| Casirivimab + Imdevimab | Neutralizing cocktail (First Generation) | Two antibodies targeting distinct RBD regions to reduce escape. | RECOVERY (benefit in seronegative hospitalized patients; reduced mortality in subgroup). | Widely used in 2021 and effective against Delta; substantially reduced activity with Omicron. |
| Regdanvimab (CT-P59) | Neutralizing (First Generation) | Anti-RBD mAb that blocks spike–ACE2 interaction. | Phase 2/3 and Phase 3 randomized trials (NCT04602000). | Demonstrated clinical benefit in pre-Omicron settings; reduced susceptibility with Omicron and later lineages constrained use. |
| Tixagevimab + Cilgavimab (Evusheld) | Pre-exposure prophylaxis (Long-acting) | Fc-modified antibodies (YTE mutations) to extend half-life (>6 months). | Early prophylaxis trials (reduced symptomatic COVID-19 risk over 6 months). | Provided protection for immunocompromised patients; reduced activity with Omicron sub-lineages limited effectiveness and use. |
| Tocilizumab | Immunomodulator (Severe Phase) | IL-6 receptor antagonist (soluble and membrane-bound), reduces inflammatory signaling. | RECOVERY, REMAP-CAP (improved survival; reduced progression to mechanical ventilation when used with corticosteroids). | Host-directed mechanism; not affected by spike mutations; remains clinically relevant in selected severe cases. |
| Sarilumab | Immunomodulator (Severe Phase) | IL-6 receptor antagonist (similar to tocilizumab). | Clinical studies/observational evidence (often used as alternative). | Used as an alternative option, including during tocilizumab shortages; host-directed mechanism. |
| Sotrovimab | Neutralizing (Later Generation) | Targets a more conserved non-RBD epitope; activity may include Fc effector contribution. | COMET-ICE (reduced progression risk in high-risk outpatients). | Active against several pre-Omicron variants and early Omicron BA.1; reduced susceptibility to BA.2/BA.4/BA.5/XBB led to restricted deployment. |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Ferrara, F.; De Berardinis, F.; Scognamiglio, M.; Zovi, A. The Shifting Paradigm of Monoclonal Antibodies in COVID-19 Management: From Early Triumphs to Viral Resistance and Future Perspectives. Antibodies 2026, 15, 48. https://doi.org/10.3390/antib15030048
Ferrara F, De Berardinis F, Scognamiglio M, Zovi A. The Shifting Paradigm of Monoclonal Antibodies in COVID-19 Management: From Early Triumphs to Viral Resistance and Future Perspectives. Antibodies. 2026; 15(3):48. https://doi.org/10.3390/antib15030048
Chicago/Turabian StyleFerrara, Francesco, Flavia De Berardinis, Manlio Scognamiglio, and Andrea Zovi. 2026. "The Shifting Paradigm of Monoclonal Antibodies in COVID-19 Management: From Early Triumphs to Viral Resistance and Future Perspectives" Antibodies 15, no. 3: 48. https://doi.org/10.3390/antib15030048
APA StyleFerrara, F., De Berardinis, F., Scognamiglio, M., & Zovi, A. (2026). The Shifting Paradigm of Monoclonal Antibodies in COVID-19 Management: From Early Triumphs to Viral Resistance and Future Perspectives. Antibodies, 15(3), 48. https://doi.org/10.3390/antib15030048