


Simple Summary
With better survival rates for patients diagnosed with cancer, more attention has been put on future risks like fertility decline due to gonadotoxic treatment. This review focusses on patient-reported outcomes (PROs) and patient experiences among adolescent and young adults (AYAs) diagnosed with cancer. An extended search showed that health care providers need to acknowledge the importance of future fertility and discuss with every AYA the potential of fertility decline. AYAs often requested a referral to a fertility specialist to be informed about fertility preservation (FP) options. They also commonly asked for more patient-specific (written) information about FP options. A clear FP pathway can prevent a delay in receiving a referral to a fertility specialist to discuss FP options and initiating FP treatment. This patient-centered approach will optimize FP experiences and establish a process to achieve long-term follow up after FP treatment.
Abstract
With better survival rates for patients diagnosed with cancer, more attention has been focused on future risks, like fertility decline due to gonadotoxic treatment. In this regard, the emphasis during counselling regarding possible preservation options is often on the treatment itself, meaning that the medical and emotional needs of patients regarding counselling, treatment, and future fertility are often overlooked. This review focuses on patient-reported outcomes (PROs) and patient experiences regarding fertility preservation (FP)—among adolescents and young adults (AYAs) with cancer. A systematic review of the literature, with a systematic search of online databases, was performed, resulting in 61 selected articles. A quality assessment was performed by a mixed methods appraisal tool (MMAT). Based on this search, three important topics emerged: initiating discussion about the risk of fertility decline, acknowledging the importance of future fertility, and recognizing the need for more verbal and written patient-specific information. In addition, patients value follow-up care and the opportunity to rediscuss FP and their concerns about future fertility and use of stored material. A clear FP healthcare pathway can prevent delays in receiving a referral to a fertility specialist to discuss FP options and initiating FP treatment. This patient-centered approach will optimize FP experiences and help to establish a process to achieve long-term follow up after FP treatment.
1. Introduction
With better survival rates for patients diagnosed with cancer in recent decades, the potential future risks of cancer treatments are now receiving more attention. One clearly defined risk is a potential decline in fertility, due to the gonadotoxic effects of chemotherapeutic agents.
In 2006, the term oncofertility was introduced by Dr. Teresa Woodruff to highlight the importance of discussing future fertility and the future reproductive health of young women before or during oncological treatments [1]. The resulting oncofertility consortium aims to provide fertility preservation options in a cancer-therapy setting [2]. With oncofertility embedded in oncological treatment policies, in combination with collaboration with multidisciplinary teams when discussing adolescent and young adult (AYA) patients diagnosed with cancer, an increasing number of patients are now being informed about the risk of infertility and their fertility preservation (FP) options. This information is essential prior to starting a gonadotoxic treatment [3,4,5,6]. FP counseling has been shown to result in less decisional regret and better quality of life [3,7], even if FP is not an option for an individual patient [8].
However, FP counseling is complex. Decisions must be made rapidly before starting a gonadotoxic treatment; under these circumstances, patients are emotionally stressed due to a recent cancer diagnosis, and their decisions are considered to be “eternally binding”. In reality, the emphasis during counseling is often on the treatment itself, with little time left to discuss the further medical and emotional needs of patients regarding counseling, treatment, and future fertility [9].
To transition from an illness-oriented to a more patient-centered approach, value-based healthcare (VBHC) was introduced as a new method for clinical decision making. In this method, all values, especially when they are complex and sometimes conflicting, are ranked [10]. These values include traditional health outcomes, such as pregnancy or complication rates, and values based on outcomes and experiences which are important to the patient.
In this review, we aim to provide an overview of patient-reported outcomes (PROs) and patient experiences regarding counseling, treatment, and future fertility in FP. This review specifically focuses on the experiences and needs of AYA patients, generally defined as cancer patients aged 15–39 years who need to start an oncological treatment. We narrowed the search to this specific group because we are currently developing and optimizing a healthcare pathway specifically for this patient group. The PROs and patient experiences defined by this patient group will be used to create patient-reported outcome measures (PROMs) and patient-reported experience measures (PREMs). These PROMs and PREMs can be incorporated in this healthcare pathway and will add value to our care.
2. Materials and Methods
We conducted a systematic review following the PRISMA guidelines [11]. This systematic review was registered and accepted for inclusion in the PROSPERO international prospective register of systematic reviews (ID CRD42023434721).
2.1. Search Strategy and Study Selection
A systematic search was conducted on 10 August 2023 of the PubMed, Embase, and Web of Science electronic databases. We used the following free text and MeSH terms: fertility preservation, sperm, oocyt*, testic*, embryo*, cryopreservation, oncofertility, assisted reproduction, neoplasms, cancer, patient-reported outcome, patient-reported experience, qualitative research, surveys, and questionnaires. The full electronic search strategy for PubMed is shown in Supplementary Table S1. The reference lists of the identified articles were manually searched for additional relevant references. A re-run of the search was performed on 27 October 2023, prior to the final analysis.
2.2. Eligibility Criteria
The inclusion criteria were original research articles in English, addressing PROs and patient experiences of AYAs regarding FP counseling, treatment, and future fertility. We included studies with AYAs, defined as patients between 15 and 39 years of age at diagnosis, or studies where >75% of the included patients were in this age range. The exclusion criteria were studies that focused on awareness of FP options or referral pathways, as well as articles about younger patients (defined as <15 years), articles about children and their parents, and articles describing research in which the main group of patients was older than 40 years of age.
The literature search was performed by a librarian and two researchers (N.K. and E.L). The results were exported to the EndNote citation manager. Duplicates were removed. Screening of the articles was performed by two researchers (N.K. and E.L.); this consisted of two stages. In the first stage, titles and abstracts were screened. In the second stage, manuscripts were reviewed in full. Any disagreements in terms of selecting studies or assessing their quality (see further) were resolved by consensus. If no agreement was obtained, the opinion of a third researcher (M.K.) was sought.
2.3. Data Analysis
Studies relevant for PROs and patient experiences that contained relevant information about female patients only, male patients only, or a combination of female and male patients were selected. The data extracted from each eligible study were recorded in a standardized extraction table including study design, country, publication year, study period, population characteristics, year of FP counselling, inclusion criteria, and relevant findings. These data were synthesized using narrative descriptions.
2.4. Quality Assessment
The quality of the selected studies was assessed using the Mixed Methods Appraisal Tool (MMAT) [12]. This is a widely used instrument for quality appraisals of quantitative, qualitative, and mixed methods studies. It can be used to assess the methodological quality of five categories of studies: qualitative research, randomized controlled trials, non-randomized trials, quantitative descriptive studies, and mixed methods studies. Each selected study was rated according to the MMAT guidelines. A qualitative assessment of each study was performed and the results were discussed by two authors (N.K and M.K). If no agreement was reached, the opinion of a third observer (E.L.) was sought to gain consensus.
3. Results
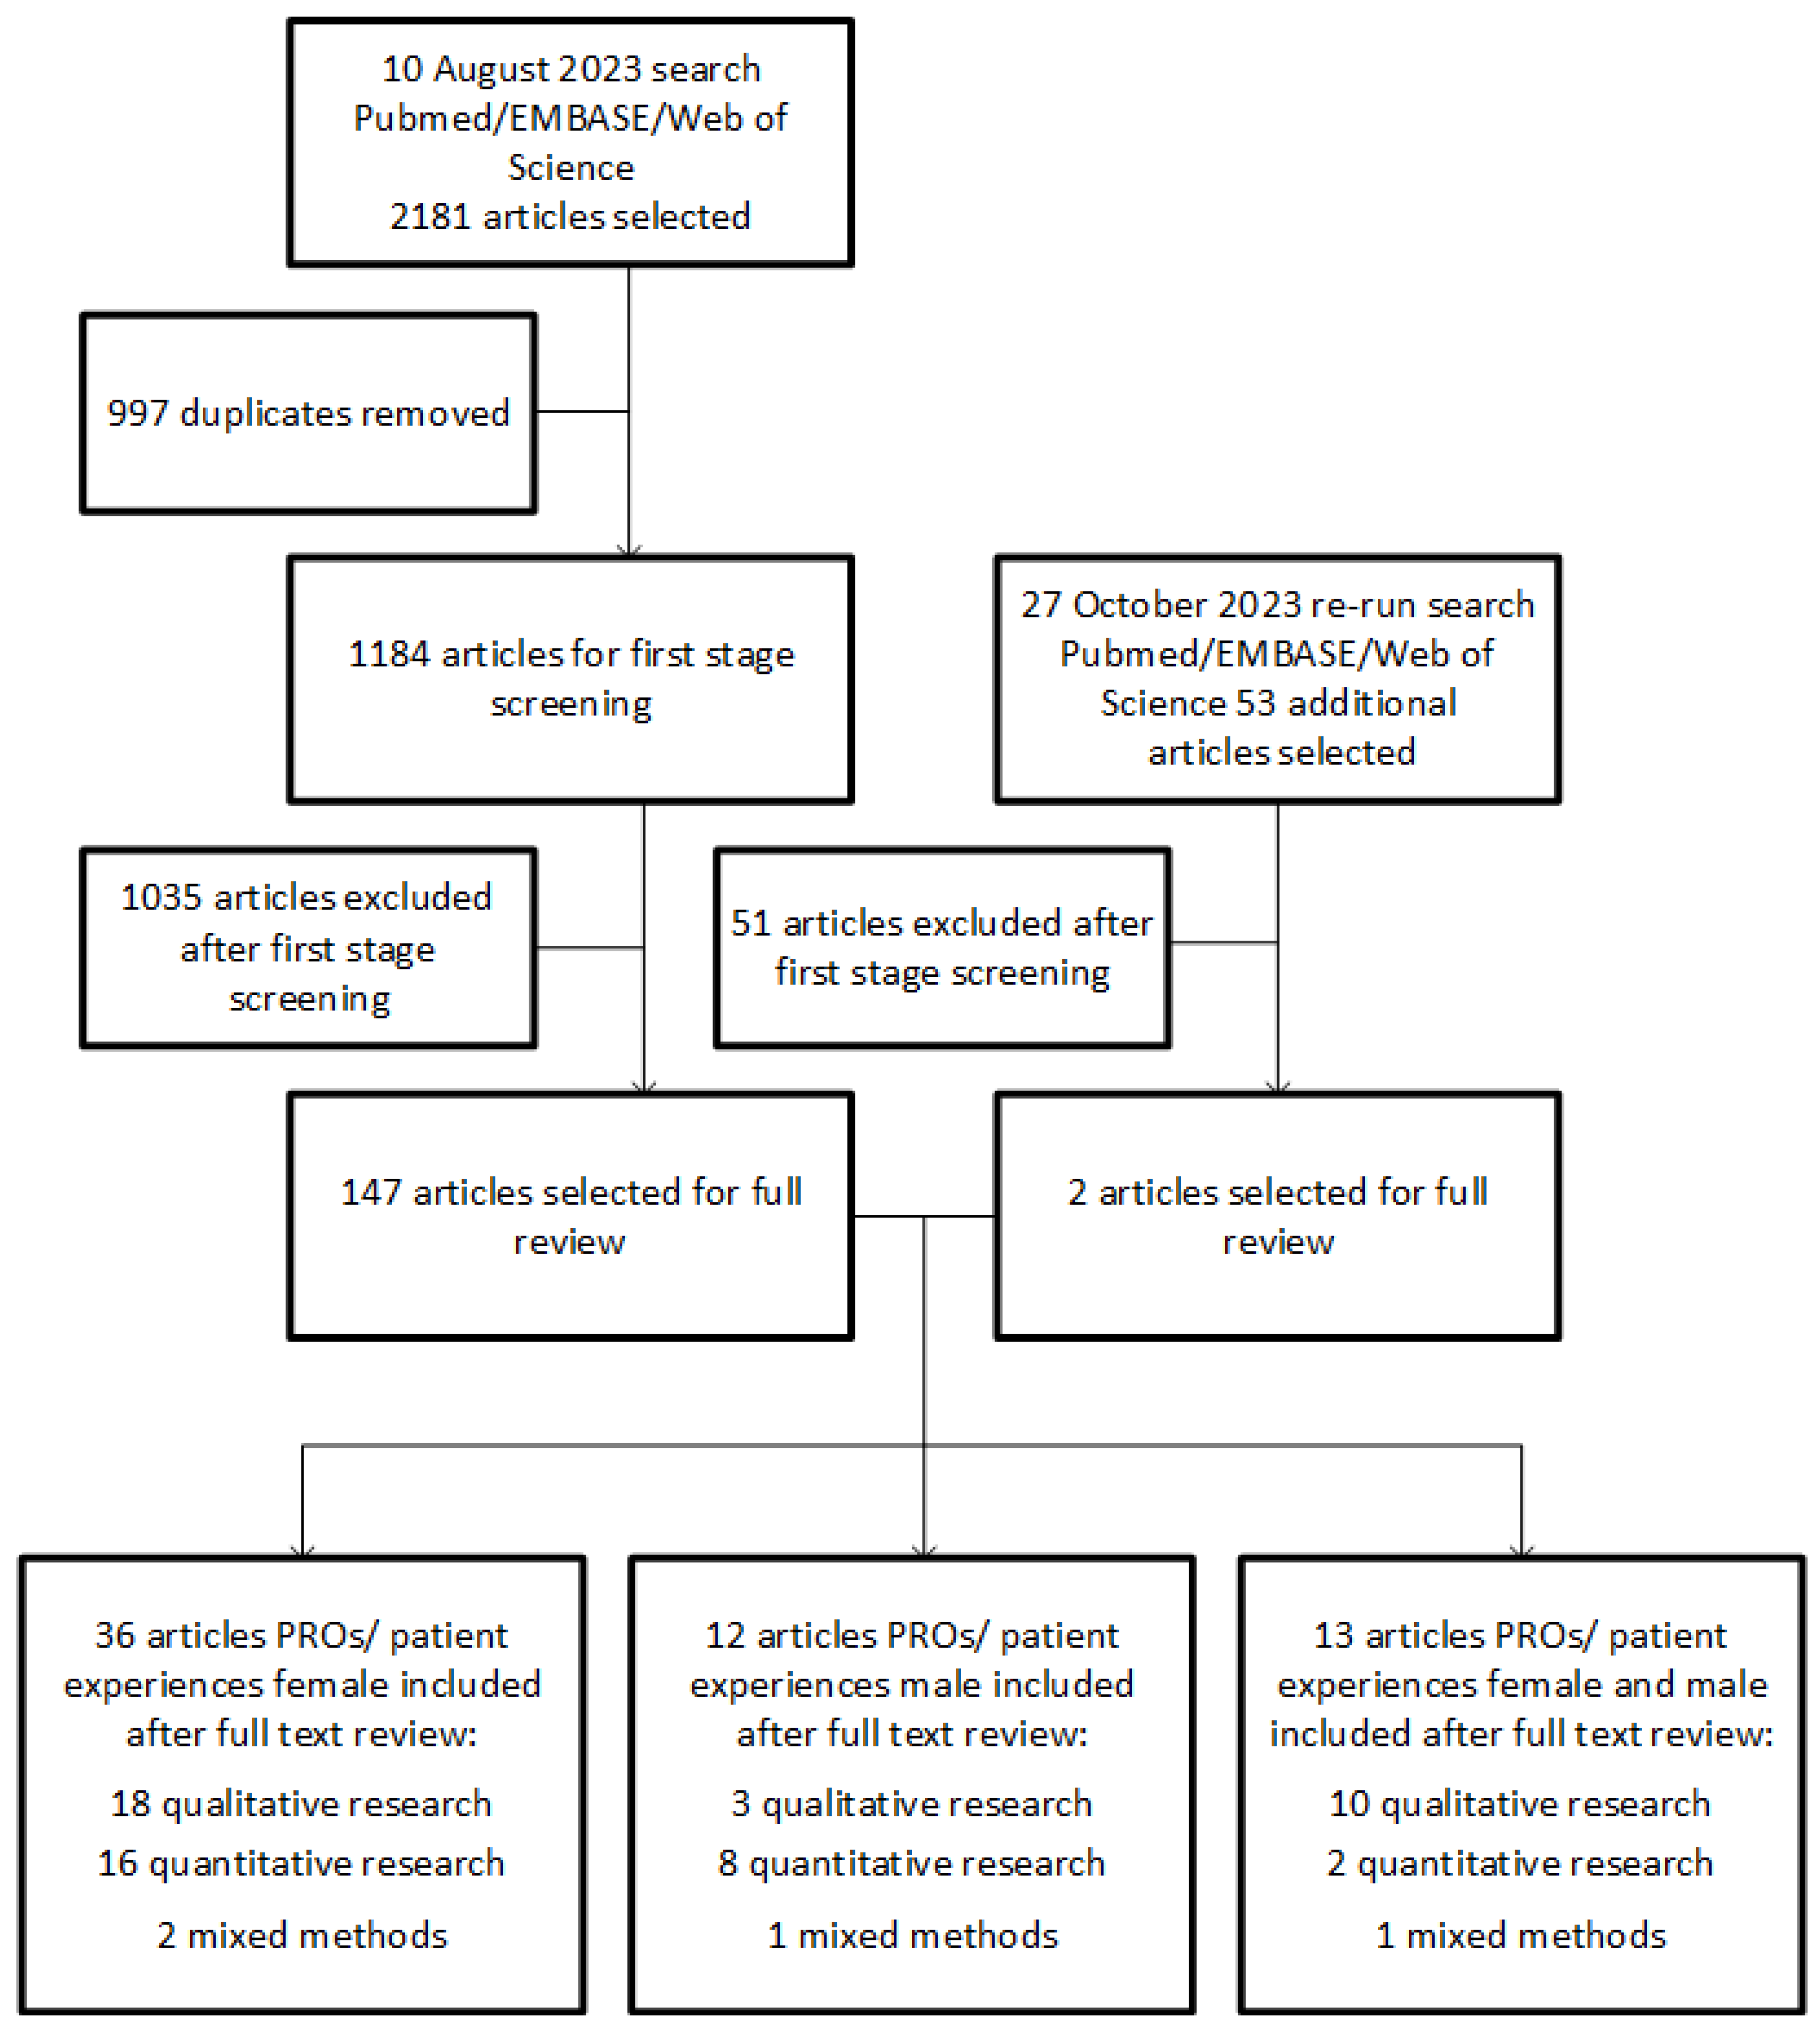
Our systematic database search retrieved a total of 2181 articles of which 1184 were unique and retained for first stage screening. After the first stage screening, 147 articles were selected for stage-two assessment. A re-run of the search was performed before finalization of the review. This resulted in 2 extra articles for full review. After the second stage screening, 61 articles that met all inclusion criteria were selected. These studies contained information regarding PROs and patient experiences; 36 were about female patients, 12 were about male patients, and 13 were about both female and male patients. Details of the study selection process are shown in the PRISMA Flow Diagram in Figure 1.
Figure 1.
PRISMA flow diagram of the study selection process.
3.1. Study Characteristics
All included studies were published between 2002 and 2023. Thirty-one qualitative studies [8,9,13,14,15,16,17,18,19,20,21,22,23,24,25,26,27,28,29,30,31,32,33,34,35,36,37,38,39,40,41], 26 quantitative studies [42,43,44,45,46,47,48,49,50,51,52,53,54,55,56,57,58,59,60,61,62,63,64,65,66,67], and 4 mixed method studies [68,69,70,71] were included. The studies had different designs, i.e., retrospective cohort, cross-sectional, and prospective cohort. In retrospective studies, patients were sampled, and often, information was collected through interviews about FP counselling and treatment. In cross-sectional studies, the outcomes and experiences of all patients were measured at or around the moment of FP counselling/treatment. In the prospective studies, patients were followed over time and data were collected at different time points for the same individuals. Most of the included studies were conducted in Western Europe (N = 26), followed by North America (N = 20), Asia (6), Australia (6), and Africa (1). In two studies, patients were recruited on different continents. In 47 studies, heterogeneous samples of different cancer diagnoses were included. Fourteen studies included patients that had the same diagnosis, most often breast cancer (79%). Two studies withheld detailed information about cancer diagnoses. The mean age of patients at diagnosis ranged from 17 to 35 years. The time between diagnosis and examination varied between a couple of weeks and up to more than 25 years. Descriptions of the key characteristics of all included studies are provided in Table 1.
Table 1.
Characteristics of included studies.
3.2. Risk of Bias
As the studies included in this research differed in their methodologies, we used the MMAT for our qualitative assessments. As shown, we included studies with qualitative, quantitative, and mixed methods designs. Sample sizes of interview studies varied from low, with the question of whether saturation for conclusions has been reached, to reasonable and good. In quantitative studies, response rates varied between 22% and 86%. Non-response bias can have an effect on the documented results. Details of our methodological analysis are described in Supplementary Table S2.
3.3. Narrative Synthesis
The data extracted from the included studies were synthesized using narrative descriptions. Table 2 summarizes the relevant PROs and patient experiences among AYAs in FP.
Table 2.
Relevant PROs and patient experiences in FP.
3.4. Starting a Conversation about Potential Fertility Decline and Referral for Fertility Preservation Counselling
3.4.1. Acknowledging the Importance of Future Fertility
Studies involving patients diagnosed with a disease whose treatment can be gonadotoxic indicated that talking about potential fertility decline is important for patients. Multiple studies reported that maintaining fertility has significant meaning for both male and female patients [25,32,53,62,64]. Latif et al. noted that male AYAs consider cancer-related infertility an important issue, as for most, fatherhood is of immense significance [32]. Schover et al. reported this specifically in men who were childless at the time of their cancer diagnosis [62]. Studies in female AYAs, on the other hand, reported that women experience fertility as an essential element of their femininity [20,25]. Kirkman et al. noted that women appreciate having the importance of FP and future childbearing recognized. If fertility concerns are not well managed, patients feel troubled [24]. Others also indicated that sometimes health care providers made treatment decisions focused on survival or extending life on behalf of the patient. Patients in these cases reported that they felt they had no choice in relation to health professional decision making. This prevented them from taking action to preserve their fertility [27,39]. Women explained that the focus of health care providers was on treating the cancer and getting practical things organized, rather than the impact of the diagnosis and treatment on the woman herself [17]. In addition, multiple studies described that female and male patients initially did not consider parenthood to be important. Going through cancer and threatened fertility had altered their perspective of how important it is to be a future parent [15,19,30,35,41]. For all these reasons, it is important to give patients with cancer the chance to think about their future parenthood [20,31]. Physicians should acknowledge the importance of future fertility [16,20,24] and, by extension, the importance of FP counselling [8,24]. Studies indicated that FP counselling should be a routine procedure when AYAs are diagnosed with cancer and are at risk of infertility [8,29,33,56]. Patients also stated that they should be provided the opportunity to preserve fertility [53,58].
3.4.2. Starting a Conversation about Potential Fertility Decline
With the acknowledgement of the importance of future fertility, the question is: when should the conversation about potential fertility decline be started? Studies show strong cross-gender support for starting the conversation about potential fertility decline due to gonadotoxic therapy early after diagnosis [20,24,28,37,53]. We need to realize that not all young cancer patients are aware of the potential fertility risks and may not even bring up the topic or ask for information [13,29]. Studies indicated that in most cases, a discussion about FP was initiated by the specialist treating the disease [13,44,45,55]. They reported that if a discussion about FP was initiated by the patient, they were already thinking parenthood or trying to conceive at the time of diagnosis [13]. Kayiira et al. mentioned that patients described that preparing to undergo cancer treatment was stressful and that there was no room to consider how the treatment would affect their future fertility. Therefore, the specialist always has to initiate the discussion [66]. In the study by Bentsen et al., however, most patients indicated that initial oncofertility counselling had not been offered by oncology specialists upon diagnosis or in subsequent consultations. The patients had to independently request specific information about FP. Some patients reported that they felt that in this situation, they were somewhat responsible for their own treatment regarding FP [8]. Bach et al. also stated that starting a conversation about this topic was difficult when a healthcare provider wanted the patient to focus more on their life-saving treatment [13]. With this lack of consideration, patients experienced dissatisfaction and regret. Insufficient initial oncofertility counselling had a huge impact on the experience of medical consultations during and after cancer treatment [8]. The absence of support and information from healthcare providers contributes to the psychological distress associated with potential fertility decline [39,71]. Crawshaw et al. noted that potential fertility decline should be discussed even if options for FP are neither available nor appropriate [37]. Anazodo et al. also reported that patients who had received FP information but did not start FP treatment valued how important this information was and reported feeling hopeful when given the opportunity to consider all aspects of life after cancer treatment at a very difficult time [33]. In a few studies, patients indicated that initiating the discussion was influenced by interpretation of social status (i.e., married, single, existing children) and that unwarranted assumptions are made about fertility desires and plans [24,27,33]. Also, (higher) age is seen as a factor for not offering FP services [9,39,52,54]. Studies, however, show that assumptions based on socio-demographic factors are not reliable determinants about a patient’s fertility desires and needs [24,32,64]. Therefore, Yee et al. recommended that physicians always address potential fertility decline and adopt a proactive approach to initiating the discussion [29]. Niemasik et al. concluded that routinely informing patients about potential fertility decline will help ensure that patients diagnosed with cancer are provided with the information they need to make an informed choice about their reproductive future [27].
3.4.3. (Early) Referral for Fertility Specialist Counselling
After starting the discussion about potential fertility decline, studies emphasized the importance for patients to consult a reproductive specialist. Consultation by a reproductive specialist shows that fertility matters [29]. Anazodo et al. reported that consultations with a fertility specialist provided an opportunity to hear about different types of FP methods and to learn more about individual FP procedures and the success rates and complications associated with various FP procedures [33]. In the study by Ehrbar et al., patients who had not had a conversation with a reproductive specialist indicated that they would have liked to have a separate consultation with an expert to discuss FP [20]. Referrals to such specialists should be sent in a timely fashion. For men, as described by Yee et al., this is vital if they are to have the opportunity to bank sufficient sperm samples for future use [64]. In women, timely referral is even more important. Unlike infertile patients, women undergoing FP often lack any previous acquaintance with the subject of fertility and infertility. The urgent nature of the treatment means that information must be conveyed in a timely fashion to help women make the best possible decisions on how to proceed regarding FP [23]. To optimize oncofertility counselling, there is a need to bridge the gap between oncology and reproductive specialists [8]. Patients suggested an automatic referral to minimize deliberation in a situation in which a lot of information has to be processed [13,24].
3.5. The Need for Verbal and Written (Patient-Specific) Information
A clear need that emerged from the articles about FP counselling and treatment was the need for more information [13,16,20,28,31,36,44,45,53,55,65,66,69,70]. The need for information can be described in two ways: the need for the timely sharing of information and the need for (patient-specific) information.
The oncologist or surgeon is often the first person who informs the patient about a potential fertility decline. In the study by Vogt et al., patients specifically noted that they desired more information from their health care providers about risks, the effects of different chemotherapy regimens, and whether a delay would increase risks [69]. This was also seen in the study by Hill et al., who noted that little specific information about the potential effects of their systemic treatment on fertility was provided before the referral to a fertility clinic. Knowing beforehand would have allowed patients to focus on their options instead of on infertility statistics [44]. A need for the timely sharing of information was also reported by women receiving extensive information at their fertility consultation; they would have liked to have received this information earlier in their care pathway, as this would have enabled them to start thinking about FP options and questions to ask the fertility specialist [29,69]. Hill et al. also mentioned this. Those authors noted that several patients reported that they would have benefitted from written information about FP options and success rates before the FP consultation [44].
Many cancer patients have limited knowledge of FP techniques [16,53]. As such, there is a need to receive clear information [40]. Patients want to be informed about their fertility risks and FP options [21,29]. Armuand et al. also described that men had a positive experience, having received information from healthcare providers conveying a feeling of importance by encouraging them to bank [34].
Written information is valued as part of consultations with health care providers [21,69]. Bach et al. described that many patients explained that they were in a state of shock at the time of FP counselling and that this prevented them from fully comprehending the technicalities. [13]. Written information can be helpful in such situations. Ehrbar et al. indicated that with written information, a patient is likely to be better informed about FP; this also prevents patients from forgetting important information [20].
Information should be easy to access. Here, a problem was reported. Patients described difficulties in finding FP information specific to cancer patients [29]. Srikanthan et al. also described the need to improve resources and the delivery of information to patients [28]. Written information regarding cancer treatment and FP options either did not exist or was too generalized.
Other studies indicated that women wanted more information about their FP options, regardless of cancer diagnosis [69], and were pleased to have been offered options for FP, including doing nothing, and having the options and their implications explained to them [24]. Wang et al. described that some patients wanted access to additional information resources, especially information relevant to their specific situation or testimonies from other patients who had undergone FP treatment [41]. On the other hand, patients also reported feeling overwhelmed by the amount of information presented to them [41] and options that were irrelevant for them, making them insecure about whether the right choice had been made regarding FP [8]. Del Valle et al. [19] noted that information was a double-edged sword. On the one hand, the patients sometimes perceived a lack of information about the process of FP and they requested more explanations; on the other hand, too much information overwhelmed them and created more anxiety. Garvelink et al. also mentioned that women were ambivalent about the information they received about FP. They seemed positive, but they also mentioned negative characteristics, e.g., issues that remained unclear to them due to a lack information or gaps in information [21]. In the study by Ehrbar et al., patients reported feeling very clearly, sometimes too comprehensively, informed about the details of FP. A large number of patients stated that they would use an additional support tool in order to find validated, objective, structured, in-depth information as a means to receive counselling [70].
3.6. The Psychological Effects of Facing Potential Fertility Decline
Studies indicated that in AYAs, a cancer diagnosis is experienced as immense: to be diagnosed with cancer and challenged to think about your fertility after just being confronted with potential death [13,18,68]. In this process, AYAs position themselves as having limited agency due to factors that are outside of their control [39,68]. Zanagnolo et al. described that infertility has a strong potential to cause distress [57]. Bentsen et al. also reported that thoughts about reduced fertility became overwhelming and frightening [15]. Some studies indicated that the way in which information of potential fertility decline is experienced depends on the life stage at the moment of diagnosis of a patient. Not having children at time of diagnosis is associated with a greater likelihood of fertility concern [50,51]. Studies involving female patients reported that among females who wanted to have children in the near future, a potential fertility decline created considerable stress and anxiety [19]. The diagnosis derailed their plans, leading them to feel overwhelmed [28]. Women challenged to think about their fertility reported that this shook the foundation of their feminine identity [25]. In addition, besides just thinking about their fertility, many female patients had never considered the possibility that they would require fertility treatment, and as such, felt overwhelmed by the pressure to make a decision [41]. Wang et al. also reported that fertility discussions and access to FP may improve patients’ emotional health and minimize ongoing fertility concerns. This would allow patients to put concerns aside at the time of diagnosis [41].
Some patients felt it would be beneficial to receive additional psychological support and counselling. They suggested that this might help patients through the decision-making process and FP treatment during this overwhelming period [24,28,41,44]. Parton et al. also reported that females diagnosed with cancer at an older reproductive age may require particular support in terms of exploring fertility options and coming to terms with the outcomes for their fertility following cancer, combined with normal age-related fertility decline [39].
3.7. Undergoing Fertility Preservation
After initiating the discussion about potential fertility decline, the process of FP starts, i.e., counselling about FP options and the decision making about whether or not to start a FP treatment.
3.7.1. Counselling
A few topics that emerged in research about experiences and needs regarding FP counselling and treatment were communication skills, organizational matters, and the cost of FP treatment.
Communication Skills
Multiple studies indicated that patients experience counselling as satisfying if a health care provider is proactive in informing the patient about the possible consequences of cancer treatment on fertility. The counselling should be informative, clear, and accurate [24,39,71]. Srikanthan et al. described that the process of decision making is experienced as a deeply personal choice and that all discussion should be sensitive to this [28]. Others added that the subject of FP counselling should be brought up with professional sensitivity, and the patient should have a choice in who is present during the discussion [8,33,37,58].
Kirkman et al. mentioned that crucial factors regarding communication were reported, i.e., being listened to and being treated with respect, no matter what the personal circumstances or desires are [24]. A health care provider should be open to hearing about personal aspirations [24]. In the study by Bentsen et al., patients also reported wanting to be met with understanding. They wanted to be taken seriously and reassured that a reproductive specialist would help as much as possible with FP and any subsequent fertility treatment. This would allow them to focus on the cancer treatment itself and convalescence [8]. Von Wolff et al. reported that counselling by a specialist about FP techniques is very satisfying to all women undergoing gonadotoxic treatment, irrespective of whether they decide for or against any specific FP treatment [56]. Canzona et al. reported that a critical turning point for FP decision making was the encountering of direct, supportive communication during initial fertility conversations with health care providers [36].
A specific point that emerged in a few studies about male AYAs was that health care providers should acknowledge that the procedure of sperm banking can be experienced as embarrassing [34,37,58]. Armuand et al. elaborated that they should give the patient the opportunity to consider who is present during the conversation about this topic. Also, the act of providing sperm in a clinical environment for fertility preservation can lead to distress, and offering alternatives, such as producing the sperm sample at home, may be helpful [34].
Organizational Matters
As mentioned before, studies reported a need for timely specialized fertility counselling and FP treatment. Inhorn et al. described that patients were grateful for well-coordinated and integrated oncofertility services with continuity of care between clinics [23]. Kirkman et al. also indicated that multidisciplinary care from oncologist, surgeons, and fertility specialists, but also nurse consultants, psychologists, and general practitioners, contributed to the quality of care [24]. It is considered helpful if the process is well organized and no organizational involvement is needed from the patient’s side [70]. Male AYAs experience FP more often as an integrated part of their cancer care [34]. Possibly because the procedure is relatively straightforward, men are more actively encouraged to consider sperm storage [9]. However, in the study van Bentsen et al., female AYAs often noted that they felt that they were falling between two different departments. They had the feeling that they had to facilitate communication about FP issues [8].
Wang et al. also reported that some patients felt out-of-place in the environment of a fertility treatment center due to their young age, single status, or male gender. They viewed these places as being primarily for females and as heterosexual couple fertility treatment centers [41].
Bentsen et al. also reported that patients expressed a wish to have an offer for consultation for their partner only at the fertility unit [8].
Costs of Fertility Preservation Treatment
Studies indicated that in countries where FP treatments are not covered by health insurers, the costs for FP can directly affect accessibility [28,35]. Costs were mentioned as a barrier for FP referral or FP procedures [30,52,67,69]. The costs that need to be considered are not just the financial burden of cancer (i.e., not being able to work) and the cost of medical treatment, but also the anticipated future costs of IVF using stored biological material [38,39,41]. In studies of Latif et al. and Yee et al. about sperm cryopreservation, costs seemed to be less of a barrier to undergoing FP treatment [32,64].
Patients for whom costs were prohibitive experienced higher decisional conflict [49]. Canzona et al. reported that difficulty weighing the decision to pursue FP because of costs is more prevalent in racial ethnic minority groups [36]. Anazodo et al. also mentioned that the financial aspect of FP or assisted reproductive treatment is a significant burden, leading to additional psychological distress and relationship problems [33].
Wang et al. and Walasik et al. stated that when FP treatments were not covered by insurers, patients felt that the costs of fertility treatments for cancer patients should be further subsidized [41,55].
3.7.2. Decision Making about a Fertility Preservation Treatment
After receiving counselling about FP options, patients need to decide whether or not to start a FP treatment. Patients described the difficulty of having to make decisions rapidly. They have to make decisions under stressful circumstances, just after a cancer diagnosis [24]. Chapple et al. described that many young men felt rushed into making a decision about sperm banking at a time when they were overburdened with information and shocked by their recent diagnosis [31]. Being forced to make this decision added to the emotional burden of coming to terms with the prospect of cancer treatment. The emotional and physical burden of cancer sometimes resulted in having reduced capacity for decision making and, with that, reduced the likelihood of undergoing FP [39]. Garvelink et al., however, noted that for some women, FP was viewed as one of many decisions to be made, and while they were already in decision-making mode, it made it easier to decide about FP [21].
Baysal et al. revealed in their study that FP decision-making among young female patients scheduled for gonadotoxic treatment is mainly based on weighing two issues: the intensity of the wish to conceive a child (in the future) and the expected burden of undergoing FP treatment [43]. Women also reported a desire to avoid future regret [22]. Garvelink et al. noted the main reason for undergoing FP was to do everything to ensure future fertility [21]. Ethical and religious reservations are important around decision making. Ethical reservations are there especially with regard to the consequences of unused material and concerns that cancer therapy might not be effective [20]. Patients value being given the choice, opportunity, and time to fully investigate FP options [71]. Although the procedure of sperm cryopreservation is relatively straightforward, men also emphasize the importance of allowing time for decision-making [34].
The process of decision making about FP was positioned as a barrier, primarily by women, who would require a longer, more physically demanding FP procedure compared to men [39]. Some women also experience an ongoing tension between ensuring their own survival through cancer treatment and the desire for a biological child [39]. Especially women with hormone-sensitive breast cancer, confronted with the threat of increased hormone levels during ovarian stimulation, shared that they experienced a threat of possible cancer growth due to FP [18,69]. A less positive experience in the decision-making process was associated with higher decisional conflict, decisional regret and lower decisional satisfaction [42,48]. A higher quality decision is positively associated with a better experience in the decision-making process. The support of a health care provider is crucial for the decisional satisfaction of patients who decided not to pursue FP [48]. Marino et al. also reported that parental or partner involvement in decision-making was considered helpful [67].
3.7.3. Experiences and Needs in Fertility Preservation Treatment
Patients that proceeded with FP treatment, reported that it is physically and emotionally challenging to have fertility treatment while simultaneously managing cancer.
In studies were experiences in FP treatment are described, a number of general topics emerged: sense of control, hope and future oriented, source of distress and the need for short term follow up.
Sense of Control
Patients describe a feeling of regaining a sense of bodily integrity and control through the reconstitution of reproductive choice [13]. It allowed patients to maintain a sense of control following the cancer diagnosis [22,39].
Hope and Future Oriented
Although men expressed fear for being infertile and experienced infertility as a loss of their manhood, they mentioned how good it was to know that they could have biological children in the future through the frozen sperm [30,34]. This sense of hope for conceiving a biological child in the future is an important aspect described by male and female patients after FP treatment was conducted [13,15,18,21,25,29,31,35,39,46,64]. It was also described as alleviating infertility related distress, thus allowing patients to feel more comfortable taking up cancer treatment [39,41,64]. Vogt at al. described that patients consider FP as positive, describing “peace of mind”, being able to “turn the negative of cancer into a positive” and “giving hope” [69]. Yee et al. similarly described that women who had cryopreserved embryos shared that this gave them hope for recovery and mental strength to fight cancer [29]. Cryopreserved material is seen as a type of insurance [13,16,23,41]. It presents an orientation towards the future. It gives patients a feeling of being directed towards survival. This is illustrated by a chance of parenthood and positive attitudes from healthcare providers generating a belief in survivorship and life after cancer [13,18,72]. Inhorn at al. documented that women who had at least one cycle of oocyte cryopreservation described this as a gift, blessing, miracle and form of empowerment [23]. Patients acknowledge however, that stored material is no guarantee for a future pregnancy [13,16,23] but maintaining the ability to conceive is significant for them [25].
Source of Distress
But FP can also be a source of distress. Dahhan et al. reported that the requirement of a cancer treatment shortly after FP causes an intense time pressure during FP [18]. This time pressure in FP was also mentioned by Bentsen et al. as “a race against time” while the cancer therapy had to start immediately [15]. Cordeiro Mitchell et al. noted that several patients described cryopreserved ovarian tissue as a sort of double-edged sword, providing hope as discussed above, but anxiety because of the uncertainty about the material (is a person going to be able to use it, will it work?) [16]. This source of distress was also mentioned by Salsman et al. in combination with an ongoing uncertainty regarding the fertility [40]. Del Valle et al. also reported that, due to the fact that the procedure of cryopreservation of ovarian tissue has to be carried out more quickly and more traumatically, the impact of the diagnosis was experienced as more intense [19].
In the research of Canzona et al. patients reported that FP is not always achieved and procedures they endure are uncomfortable and embarrassing [35]. Wang et al. also described the burden of FP treatment, disappointment and ongoing concerns, for example, a small number of oocytes able to be collected [41]. After failed FP attempts, Canzona et al. mentioned that patients are unsure future attempts will be successful [35]. Also distress about unknown fertility outcomes (no guarantee) and the burden of their partner (in particular female partners) potentially undergoing fertility treatment are described [39]. Single women confronted with a cancer diagnosis and FP are also worried about the fear of rejection by potential partners [17,25]. This is in line with the reported anxiety around current and future romantic relationships research of Canzona et al. They also reported sadness, guilt and jealousy surrounding friendships [35].
Short Term Follow Up Consultation after Fertility Preservation
Bach et al. described that in a crisis and information overload at the point of diagnosis, patients reported limited recollection or understanding of information received at the initial counselling [13]. Also in the study of Ehrbar et al. patients stated to be felt overwhelmed by the immense amount of information. The majority mentioned that it would be helpful to know that reproductive health can be revisited later [70]. Patients in the study of Yee et al. also indicates that follow up after FP was important. It provided in-depth information about sperm quality and better understanding of the results prior to the start of oncological treatment [64].
3.8. Worries around Future Fertility and Increase Cancer Risks
Patients’ desire for future father- or motherhood are main determinants associated with undergoing FP treatments [64]. Anazodo et al. mentioned that many patients reported more anxiety about their fertility potential after cancer treatment than at the time of diagnosis and FP [33]. Walasik et al. described that patients were mostly concerned about the safety of having children after oncological treatment [55]. Canzona et al. stated that patients have worries and uncertainty that cancer and/or treatment makes it less likely for them to be healthy enough to raise future children [35]. Despite anxieties about surviving to see their children growing up, 24% of childless men felt that having cancer had increased their wish to have children [62]. Wang et al. and Canzona et el. reported concerns about the impact of chemotherapy on the consequent health of future children [35,41]. Schover et al. stated that 31% of the patients in their research believed that their children would definitely be at increased risk for cancer. A smaller percentage, about one fourth worried that their past cancer treatment could affect the health of children conceived afterward [62]. Zhang et al. [65] and Achille et al. [30] also stated the concern about the possibility of transmitting a disease to their progeny. Women carrying BRCA mutations were more likely to have increased concern about future children inheriting increased cancer risk. This highlights the importance of incorporating tailored, risk-mitigating recommendations into fertility counseling [47,51,69]. In women with estrogen-sensitive breast cancer there was the concern of how to achieve a safe pregnancy in the future [41,69]. This safety concern was also mentioned in association with risks involved with ovarian tissue transplantation. Ovarian tissue (re)connects the patient with their disease in ways that frozen oocytes or embryos do not. Worries about risks in post-cancer reproduction were especially prevalent among women who had estrogen-sensitive breast cancer, those who had tested positive for BRCA genes and those, who had for instance, sarcomas in the lower parts of the body [13]. Another concern mentioned is about not being able to take care of their children in case of disease relapse [51].
A different concern emerged is the effect of cancer diagnosis on psychosocial aspects. Anazoda et al. mentioned that the fear of being infertile had a negative impact on starting intimate relationships [33]. In the research of Salsman et al. patients reported that a cancer diagnosis and potential infertility would make them less desirable partners. Preserving their fertility was a priority to mitigate those fears [40].
3.9. Follow Up after Fertility Preservation
When FP treatment has been completed, consultation with the fertility specialist is, most of the time, ended. However, patients want health care providers to be aware of and discuss the impact of chemotherapy and infertility after completion of active treatment. The negative impact of chemotherapy on quality of life during survivorship remains important. Respondents endorsed limited discussions with health care providers about how and when to engage with fertility specialists after chemotherapy, and possible fertility screening or surveillance that can be undertaken [14,28]. Bentsen et al. compared this subsequent waiting time to a marathon. Not until the waiting time was over, the participants found out the consequences of the cancer treatment [15]. Many studies list the importance of informational follow ups to lower distress in patients. Patients experience distress when they have less knowledge about reproductive biology. Patients want consultation regarding their fertility concerns and report uncertainty about the time range for fertility treatment after cancer therapy. Patients also notify that they were in doubt whether they still belonged to the fertility unit or not, and where to obtain information. Distress can also be caused by questioning whether to continue the storage of the preserved material [8,13,16]. Bentsen et al. reported that it is advised to offer the possibility of fertility assessment after cancer treatment [8]. Benedict et al. stated that provider-initiated discussions relieved patients form the burden of bringing up concerns themselves. Patients worry about missing critical information or reproductive time window and fear early menopause [14]. Bach et al. also reported a need for interventions to handle and reduce fears regarding risks of re-transplanting ovarian tissue and post-cancer reproduction within a clinical care pathway of fertility preservation and post-cancer reproduction [13]. Patients in the research of Ehrbar et al. clearly stated interest in aspects beyond FP, such as fertility and contraception, sexuality, masculinity, and impact on couple life [70]. Anazodo et al. reported that FP consultation in the survivorship period is seen as an opportunity to talk about sexual health, safe sex practice and symptoms of sexual dysfunction and to receive advise and support about fertility-related psychosocial distress [33]. Benedict et al. also reported a need for emotional support in post-treatment care where counselling can help with uncertainty and distress [14]. Kirkman et al. reported to be alert to the need for continuing psychological care as women confront the fear of recurrence and grief about lost fertility [24].
4. Discussion
This systematic review was conducted to get an overview of patient reported outcomes (PROs) and patient experiences regarding the counselling, treatment and future fertility in FP in adolescents and young adults (AYAs) with cancer. Various studies report on PROs and patient experiences in FP in AYAs in the intense situation of being diagnosed with cancer but also being confronted with potential risk of infertility due to the necessary treatment. Relevant PROs and patient experiences with FP counselling are summarized in Table 2 and include a proactive approach in initiating the conversation about potential fertility decline by oncological specialists when there is a need to start a gonadotoxic cancer treatment. All AYAs should have the opportunity for an open discussion about the possibilities for FP and early referral to a fertility specialist is essential. In addition, patients report the need for additional patient specific information, emphasizing the value of verbal and written patient information about FP. Finally, there is a need for follow up in these patients after the FP treatment has been completed.
The acknowledgement of the importance of future fertility was also confirmed in the review of Taylor et al. where they defined this PRO as “fertility in trust” as an obligation of the health care provider to recognize the long-term importance of fertility. Here the long-term effect on fertility is influenced by short term decisions [73]. In addition, some AYA believe the possibility of FP is an expression of professional belief that they have a future [37].
This review shows a need for clear information provision in the whole process of counselling, treatment, but specifically in follow up after FP counselling (and treatment). The need for information is mentioned in reviews of Daly et al. [74] and Linnane et al. [75] on factors affecting patient FP decision making, where information provision was often perceived as inadequate or unclear. Recently, Clasen et al. also mentioned the under reporting of regrets and concerns after FP counselling, possibly explaining the variable satisfaction with fertility information [76]. The focus of these reviews, however, was narrowed to the decision-making process in FP. Our review informs that the need for information is more extensive. Where consultation with a fertility specialist after FP counselling and FP treatment most often ends, patients show specific needs for further follow up. The information overload after a recent cancer diagnosis demands later revisiting and after a cancer treatment more information concerning future fertility is needed.
The need for FP follow up care is also mentioned by Gonçalves et al. They focused on perspectives of FP in young women with gynecological cancer and described the need for follow up care [77]. Macklon and Fauser concluded that this follow up after FP is important; issues related to the use of the stored material could be addressed at these visits as well as safety concerns that some of the patients may have [78].
Of course, results of included articles in our review could be influenced by different factors. First, experiences in FP are possibly influenced by the country of residence. Accessibility of oncofertility services can be influenced by multiple factors, including financial aspects of FP treatment [70]. In a country where there is no reimbursement, costs of FP treatment could be an obstacle. Our review showed that not all studies indicated that costs are a factor in FP decision making and FP treatment. This was however reported in studies regarding sperm cryopreservation [32,64]. In this treatment costs to conduct FP are relatively low. Selection bias is questioned where included patients already underwent sperm cryopreservation [64]. Costs for cryopreservation of oocytes on the other hand are considerably higher and absence of reimbursement could have a great effect on the decision regarding FP. In our review a large amount of included studies are conducted in high income countries. This could possibly lead to a narrow view and with this missing of other patients’ specific needs in FP counselling and FP treatment.
Secondly, the year of performed FP counselling and treatment of included patients in a study is also of importance. The field of FP options has grown hugely in the last years. On one hand because of the increasing recognition of the importance of potential loss because of gonadotoxic treatment, and on the other hand because of increasing technologies of preservation options. Where ovarian tissue cryopreservation and transplantation was described as a scientific treatment ten years ago, nowadays it is a standard form of care. And where embryo cryopreservation was, a long time, the standard procedure for FP in women, with no opportunity for patients without a male partner, this has been changed with the introduction of vitrification of oocytes over the last decade. In addition, the proportion of FP discussion and fertility specialist consultation has changed with the introduction of newer methods [52]. Finally, with the embedding of FP counselling and treatment in oncological protocols, referral patterns have changed over time towards better accessibility of FP for patients. In this context we also have to take into account that differences in experiences of patients could have been influenced through timing of the treatment. Peddie et al. for example described that women were feeling negative about FP because they didn’t have the opportunity due to less FP possibilities at that time [9]. Unfortunately 40% of the included studies in this review didn’t describe the year of FP counselling and treatment and since others have a wide distribution in year of FP counselling and treatment it is difficult to show differences in PROs and patient’s experiences in FP over time between the different studies.
Lastly, there were differences in patient populations between the studies. Some studies included only patients with the same cancer diagnosis, others had multiple cancer diagnoses in their inclusion. Another difference between the studies was the time between diagnosis and performed examination. This time varied between a couple of weeks up to more than 25 years. Next to gender and with that potential FP options, all these differences could possibly influence the reported outcomes and experiences.
In this study we have decided to focus on AYAs experiences. Of course, FP treatments are also available and needed for prepuberal children or (male) patients ≥40 years. However, we decided to exclude these patients since other aspects, such as diminished ovarian or sperm quality, could interfere with the possibilities of FP. Specifically, in prepuberal girls and boys FP possibilities are complex or experimental. Moreover, patient reported outcome measures of FP can be difficult to define with these young patients and also possibly the influence of their parents. Still, talking about potential fertility decline and options of FP is essential in these groups [79].
5. Conclusions
Being confronted with a potential life-threatening disease and simultaneously have to consider FP treatment is an intense situation for AYAs diagnosed with cancer. In this review we summarized the published PROs and patient experiences regarding the counselling, FP treatment and future fertility. This includes the need for patients to acknowledge the importance of future fertility, more patient specific information and the need for follow up after oncological treatment that has a risk of fertility decline.
As mentioned by del Valle et al. despite advances and increasing awareness about the importance of the integral treatment of cancer and FP, there is a lack of knowledge regarding patient experiences and needs in this process [19]. We believe a clear FP pathway can prevent delays in receiving a referral to a fertility specialist to discuss FP options and initiating FP treatment. By measuring the patient reported outcomes and patient reported experiences (PROMs and PREMs) and incorporating these in a FP pathway, experiences around FP will be optimized and a process established to achieve long-term follow up after FP treatment.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/cancers15245828/s1. Supplementary Table S1. PubMed search and Supplementary Table S2 Quality assessment MMAT.
Author Contributions
Conceptualization, E.E.L.O.L.; Methodology, M.M.t.K. and E.E.L.O.L.; Software, not applicable; Validation, N.F.K. and E.E.L.O.L.; Formal Analysis, N.F.K., M.M.t.K. and E.E.L.O.L.; Investigation, N.F.K., M.M.t.K. and E.E.L.O.L.; Resources, not applicable.; Data Curation, N.F.K.; Writing—Original Draft Preparation, N.F.K.; Writing—Review & Editing, N.F.K., M.M.t.K. and E.E.L.O.L.; Visualization, N.F.K.; Supervision, not applicable; Project Administration, not applicable; Funding Acquisition, not applicable. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Acknowledgments
The authors would like to thank J.W.M. Plevier for her support during the search strategy.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Woodruff, T.K. The emergence of a new interdiscipline: Oncofertility. Cancer Treat. Res. 2007, 138, 3–11. [Google Scholar] [PubMed]
- Woodruff, T.K. Oncofertility: A grand collaboration between reproductive medicine and oncology. Reproduction 2015, 150, S1–S10. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Letourneau, J.M.; Ebbel, E.E.; Katz, P.P.; Katz, A.; Ai, W.Z.; Chien, A.J.; Melisko, M.E.; Cedars, M.I.; Rosen, M.P. Pretreatment fertility counseling and fertility preservation improve quality of life in reproductive age women with cancer. Cancer 2012, 118, 1710–1717. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fertility preservation and reproduction in patients facing gonadotoxic therapies: An Ethics Committee opinion. Fertil. Steril. 2018, 110, 380–386. [CrossRef] [Scilit] [PubMed]
- Anderson, R.A.; Amant, F.; Braat, D.; D’Angelo, A.; Chuva de Sousa Lopes, S.M.; Demeestere, I.; Dwek, S.; Frith, L.; Lambertini, M.; Maslin, C.; et al. ESHRE guideline: Female fertility preservation. Hum. Reprod. Open 2020, 2020, hoaa052. [Google Scholar] [PubMed]
- Zaami, S.; Montanari Vergallo, G.; Moscatelli, M.; Napoletano, S.; Sernia, S.; La Torre, G. Oncofertility: The importance of counseling for fertility preservation in cancer patients. Eur. Rev. Med. Pharmacol. Sci. 2021, 25, 6874–6880. [Google Scholar] [PubMed]
- Skaczkowski, G.; White, V.; Thompson, K.; Bibby, H.; Coory, M.; Orme, L.M.; Conyers, R.; Phillips, M.B.; Osborn, M.; Harrup, R.; et al. Factors influencing the provision of fertility counseling and impact on quality of life in adolescents and young adults with cancer. J. Psychosoc. Oncol. 2018, 36, 484–502. [Google Scholar] [CrossRef] [Scilit]
- Bentsen, L.; Pappot, H.; Hjerming, M.; Colmorn, L.B.; Macklon, K.T.; Hanghoj, S. How do young women with cancer experience oncofertility counselling during cancer treatment? A qualitative, single centre study at a Danish tertiary hospital. Cancers 2021, 13, 1355. [Google Scholar] [CrossRef] [Scilit]
- Peddie, V.L.; Porter, M.A.; Barbour, R.; Culligan, D.; MacDonald, G.; King, D.; Horn, J.; Bhattacharya, S. Factors affecting decision making about fertility preservation after cancer diagnosis: A qualitative study. BJOG Int. J. Obstet. Gynaecol. 2012, 119, 1049–1057. [Google Scholar] [CrossRef] [Scilit]
- Porter, M.E.; Teisberg, E.O. Redefining Health Care: Creating Valie-Based Competition on Results; Harvard Business Press: Boston, MA, USA, 2006. [Google Scholar]
- Moher, D.; Liberati, A.; Tetzlaff, J.; Altman, D.G. Preferred reporting items for systematic reviews and meta-analyses: The PRISMA statement. J. Clin. Epidemiol. 2009, 62, 1006–1012. [Google Scholar] [CrossRef] [Scilit]
- Hong, Q.N.; Fàbregues, S.; Bartlett, G.; Boardman, F.; Cargo, M.; Dagenais, P.; Gagnon, M.-P.; Griffiths, F.; Nicolau, B.; O’Cathain, A.; et al. The mixed methods appraisal tool (MMAT) version 2018 for information professionals and researchers. Educ. Inf. Int. Rev. Educ. Train. Libr. Inf. Sci. 2018, 34, 285–291. [Google Scholar] [CrossRef] [Scilit]
- Bach, A.S.; Schmidt, K.T.; Kristensen, S.G. Futures and fears in the freezer: Danish women’s experiences with ovarian tissue cryopreservation and transplantation. Reprod. BioMed. Online 2020, 41, 555–565. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Benedict, C.; Nieh, J.L.; Hahn, A.L.; McCready, A.; Diefenbach, M.; Ford, J.S. “Looking at future cancer survivors, give them a roadmap”: Addressing fertility and family-building topics in post-treatment cancer survivorship care. Support. Care Cancer 2021, 29, 2203–2213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bentsen, L.; Pappot, H.; Hjerming, M.; Hanghøj, S. Thoughts about fertility among female adolescents and young adults with cancer: A qualitative study. Support. Care Cancer 2023, 31, 421. [Google Scholar] [CrossRef] [Scilit]
- Cordeiro Mitchell, C.N.; Whiting-Collings, L.J.; Christianson, M.S. Understanding Patients’ Knowledge and Feelings Regarding Their Cryopreserved Ovarian Tissue: A Qualitative Interviewing Study. J. Adolesc. Young Adult Oncol. 2020, 9, 502–507. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Corney, R.; Puthussery, S.; Swinglehurst, J. The stressors and vulnerabilities of young single childless women with breast cancer: A qualitative study. Eur. J. Oncol. Nurs. 2014, 18, 17–22. [Google Scholar] [CrossRef] [Scilit]
- Dahhan, T.; van der Veen, F.; Bos, A.M.E.; Goddijn, M.; Dancet, E.A.F. The experiences of women with breast cancer who undergo fertility preservation. Hum. Reprod. Open 2021, 2021, hoab018. [Google Scholar] [CrossRef] [Scilit]
- Del Valle, L.; Corchón, S.; Palop, J.; Rubio, J.M.; Celda, L. The experience of female oncological patients and fertility preservation: A phenomenology study. Eur. J. Cancer Care 2022, 31, e13757. [Google Scholar] [CrossRef] [Scilit]
- Ehrbar, V.; Urech, C.; Alder, J.; Harringer, K.; Zanetti Dällenbach, R.; Rochlitz, C.; Tschudin, S. Decision-making about fertility preservation-qualitative data on young cancer patients’ attitudes and needs. Arch. Women’s Ment. Health 2016, 19, 695–699. [Google Scholar] [CrossRef] [Scilit]
- Garvelink, M.M.; ter Kuile, M.M.; Bakker, R.M.; Geense, W.J.; Jenninga, E.; Louwé, L.A.; Hilders, C.G.; Stiggelbout, A.M. Women’s experiences with information provision and deciding about fertility preservation in the Netherlands: ‘Satisfaction in general, but unmet needs’. Health Expect. 2015, 18, 956–968. [Google Scholar] [CrossRef] [Scilit]
- Hershberger, P.E.; Sipsma, H.; Finnegan, L.; Hirshfeld-Cytron, J. Reasons Why Young Women Accept or Decline Fertility Preservation After Cancer Diagnosis. J. Obstet. Gynecol. Neonatal Nurs. 2016, 45, 123–134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Inhorn, M.C.; Birenbaum-Carmeli, D.; Westphal, L.M.; Doyle, J.; Gleicher, N.; Meirow, D.; Raanani, H.; Dirnfeld, M.; Patrizio, P. Medical egg freezing: The importance of a patient-centered approach to fertility preservation. J. Assist. Reprod. Genet. 2018, 35, 49–59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kirkman, M.; Stern, C.; Neil, S.; Winship, I.; Mann, G.B.; Shanahan, K.; Missen, D.; Shepherd, H.; Fisher, J.R. Fertility management after breast cancer diagnosis: A qualitative investigation of women’s experiences of and recommendations for professional care. Health Care Women Int. 2013, 34, 50–67. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Komatsu, H.; Yagasaki, K.; Shoda, R.; Chung, Y.; Iwata, T.; Sugiyama, J.; Fujii, T. Repair of the threatened feminine identity: Experience of women with cervical cancer undergoing fertility preservation surgery. Cancer Nurs. 2014, 37, 75–82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Komatsu, H.; Yagasaki, K.; Yamauchi, H. Fertility decision-making under certainty and uncertainty in cancer patients. Sex. Reprod. Healthc. 2018, 15, 40–45. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Niemasik, E.E.; Letourneau, J.; Dohan, D.; Katz, A.; Melisko, M.; Rugo, H.; Rosen, M. Patient perceptions of reproductive health counseling at the time of cancer diagnosis: A qualitative study of female California cancer survivors. J. Cancer Surviv. 2012, 6, 324–332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Srikanthan, A.; Ethier, J.L.; Amir, E. The Voices of Young Women with Breast Cancer: Providing Support and Information for Improved Fertility Preservation Discussions. J. Adolesc. Young Adult Oncol. 2019, 8, 547–553. [Google Scholar] [CrossRef] [Scilit]
- Yee, S.; Abrol, K.; McDonald, M.; Tonelli, M.; Liu, K.E. Addressing oncofertility needs: Views of female cancer patients in fertility preservation. J. Psychosoc. Oncol. 2012, 30, 331–346. [Google Scholar] [CrossRef] [Scilit]
- Achille, M.A.; Rosberger, Z.; Robitaille, R.; Lebel, S.; Gouin, J.P.; Bultz, B.D.; Chan, P.T. Facilitators and obstacles to sperm banking in young men receiving gonadotoxic chemotherapy for cancer: The perspective of survivors and health care professionals. Hum. Reprod. 2006, 21, 3206–3216. [Google Scholar] [CrossRef] [Scilit]
- Chapple, A.; Salinas, M.; Ziebland, S.; McPherson, A.; MacFarlane, A. Fertility issues: The perceptions and experiences of young men recently diagnosed and treated for cancer. J. Adolesc. Health 2007, 40, 69–75. [Google Scholar] [CrossRef] [Scilit]
- Latif, N.; Ali, N. Patient and Physician Perspective on Sperm Banking to Overcome Post-Treatment Infertility in Young Cancer Patients in Pakistan. J. Adolesc. Young Adult Oncol. 2019, 8, 54–60. [Google Scholar] [CrossRef] [Scilit]
- Anazodo, A.C.; Gerstl, B.; Stern, C.J.; McLachlan, R.I.; Agresta, F.; Jayasinghe, Y.; Cohn, R.J.; Wakefield, C.E.; Chapman, M.; Ledger, W.; et al. Utilizing the Experience of Consumers in Consultation to Develop the Australasian Oncofertility Consortium Charter. J. Adolesc. Young Adult Oncol. 2016, 5, 232–239. [Google Scholar] [CrossRef] [Scilit]
- Armuand, G.M.; Wettergren, L.; Rodriguez-Wallberg, K.A.; Lampic, C. Women more vulnerable than men when facing risk for treatment-induced infertility: A qualitative study of young adults newly diagnosed with cancer. Acta Oncol. 2015, 54, 243–252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Canzona, M.R.; Victorson, D.E.; Murphy, K.; Clayman, M.L.; Patel, B.; Puccinelli-Ortega, N.; McLean, T.W.; Harry, O.; Little-Greene, D.; Salsman, J.M. A conceptual model of fertility concerns among adolescents and young adults with cancer. Psychooncology 2021, 30, 1383–1392. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Canzona, M.R.; Murphy, K.; Victorson, D.; Harry, O.; Clayman, M.L.; McLean, T.W.; Golden, S.L.; Patel, B.; Strom, C.; Little-Greene, D.; et al. Fertility Preservation Decisional Turning Points for Adolescents and Young Adults With Cancer: Exploring Alignment and Divergence by Race and Ethnicity. JCO Oncol. Pract. 2023, 19, 509–515. [Google Scholar] [CrossRef] [Scilit]
- Crawshaw, M.A.; Glaser, A.W.; Hale, J.P.; Sloper, P. Male and female experiences of having fertility matters raised alongside a cancer diagnosis during the teenage and young adult years. Eur. J. Cancer Care 2009, 18, 381–390. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Levin, N.J.; Tan, C.Y.; Stelmak, D.; Iannarino, N.T.; Zhang, A.A.; Ellman, E.; Herrel, L.A.; Walling, E.B.; Moravek, M.B.; Chugh, R.; et al. Banking on Fertility Preservation: Financial Concern for Adolescent and Young Adult Cancer Patients Considering Oncofertility Services. J. Adolesc. Young Adult Oncol. 2023, 12, 710–717. [Google Scholar] [CrossRef] [Scilit]
- Parton, C.; Ussher, J.M.; Perz, J. Hope, burden or risk: A discourse analytic study of the construction and experience of fertility preservation in the context of cancer. Psychol. Health 2019, 34, 456–477. [Google Scholar] [CrossRef] [Scilit]
- Salsman, J.M.; Yanez, B.; Snyder, M.A.; Avina, A.R.; Clayman, M.L.; Smith, K.N.; Purnell, K.; Victorson, D. Attitudes and practices about fertility preservation discussions among young adults with cancer treated at a comprehensive cancer center: Patient and oncologist perspectives. Support. Care Cancer 2021, 29, 5945–5955. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Logan, S.; Stern, K.; Wakefield, C.E.; Cohn, R.J.; Agresta, F.; Jayasinghe, Y.; Deans, R.; Segelov, E.; McLachlan, R.I.; et al. Supportive oncofertility care, psychological health and reproductive concerns: A qualitative study. Support. Care Cancer 2020, 28, 809–817. [Google Scholar] [CrossRef] [Scilit]
- Bastings, L.; Baysal, Ö.; Beerendonk, C.C.; IntHout, J.; Traas, M.A.; Verhaak, C.M.; Braat, D.D.; Nelen, W.L. Deciding about fertility preservation after specialist counselling. Hum. Reprod. 2014, 29, 1721–1729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Baysal, Ö.; Bastings, L.; Beerendonk, C.C.; Postma, S.A.; IntHout, J.; Verhaak, C.M.; Braat, D.D.; Nelen, W.L. Decision-making in female fertility preservation is balancing the expected burden of fertility preservation treatment and the wish to conceive. Hum. Reprod. 2015, 30, 1625–1634. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hill, K.A.; Nadler, T.; Mandel, R.; Burlein-Hall, S.; Librach, C.; Glass, K.; Warner, E. Experience of young women diagnosed with breast cancer who undergo fertility preservation consultation. Clin. Breast Cancer 2012, 12, 127–132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ko, J.K.Y.; Cheung, C.S.Y.; Cheng, H.H.Y.; Yung, S.S.F.; Ng, T.Y.; Tin, W.W.Y.; Yuen, H.Y.; Lam, M.H.C.; Chan, A.S.Y.; Fung, S.W.W.; et al. Knowledge, attitudes and intention on fertility preservation among breast cancer patients. Sci. Rep. 2023, 13, 9645. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leflon, M.; Rives-Feraille, A.; Letailleur, M.; Petrovic, C.H.; Martin, B.; Marpeau, L.; Jardin, F.; Aziz, M.; Stamatoulas-Bastard, A.; Dumont, L.; et al. Experience, and gynaecological and reproductive health follow-up of young adult women who have undergone ovarian tissue cryopreservation. Reprod. BioMed. Online 2022, 45, 913–922. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lewinsohn, R.; Zheng, Y.; Rosenberg, S.M.; Ruddy, K.J.; Tamimi, R.M.; Schapira, L.; Peppercorn, J.; Borges, V.F.; Come, S.; Snow, C.; et al. Fertility Preferences and Practices Among Young Women With Breast Cancer: Germline Genetic Carriers Versus Noncarriers. Clin. Breast Cancer 2022, 23, 317–323. [Google Scholar] [CrossRef] [Scilit]
- Melo, C.; Fonseca, A.; Moura-Ramos, M.; Almeida-Santos, T.; Canavarro, M.C. Female cancer patients’ perceptions of the fertility preservation decision-making process: An exploratory prospective study. J. Psychosoc. Oncol. 2018, 36, 364–381. [Google Scholar] [CrossRef] [Scilit]
- Mersereau, J.E.; Goodman, L.R.; Deal, A.M.; Gorman, J.R.; Whitcomb, B.W.; Su, H.I. To preserve or not to preserve: How difficult is the decision about fertility preservation? Cancer 2013, 119, 4044–4050. [Google Scholar] [CrossRef] [Scilit]
- Ruddy, K.J.; Gelber, S.I.; Tamimi, R.M.; Ginsburg, E.S.; Schapira, L.; Come, S.E.; Borges, V.F.; Meyer, M.E.; Partridge, A.H. Prospective study of fertility concerns and preservation strategies in young women with breast cancer. J. Clin. Oncol. 2014, 32, 1151–1156. [Google Scholar] [CrossRef] [Scilit]
- Ruggeri, M.; Pagan, E.; Bagnardi, V.; Bianco, N.; Gallerani, E.; Buser, K.; Giordano, M.; Gianni, L.; Rabaglio, M.; Freschi, A.; et al. Fertility concerns, preservation strategies and quality of life in young women with breast cancer: Baseline results from an ongoing prospective cohort study in selected European Centers. Breast 2019, 47, 85–92. [Google Scholar] [CrossRef] [Scilit]
- Sauerbrun-Cutler, M.T.; Pandya, S.; Recabo, O.; Raker, C.; Clark, M.A.; Robison, K. Survey of young women with breast cancer to identify rates of fertility preservation (FP) discussion and barriers to FP care. J. Assist. Reprod. Genet. 2023, 40, 2003–2011. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Urech, C.; Ehrbar, V.; Boivin, J.; Müller, M.; Alder, J.; Zanetti Dällenbach, R.; Rochlitz, C.; Tschudin, S. Knowledge about and attitude towards fertility preservation in young female cancer patients: A cross-sectional online survey. Hum. Fertil. 2018, 21, 45–51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van den Berg, M.; Kaal, S.E.J.; Schuurman, T.N.; Braat, D.D.M.; Mandigers, C.; Tol, J.; Tromp, J.M.; van der Vorst, M.; Beerendonk, C.C.M.; Hermens, R. Quality of integrated female oncofertility care is suboptimal: A patient-reported measurement. Cancer Med. 2023, 12, 2691–2701. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Walasik, I.; Falis, M.; Płaza, O.; Szymecka-Samaha, N.; Szymusik, I. Polish Female Cancer Survivors’ Experiences Related to Fertility Preservation Procedures. J. Adolesc. Young Adult Oncol. 2023, 12, 727–734. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- von Wolff, M.; Giesecke, D.; Germeyer, A.; Lawrenz, B.; Henes, M.; Nawroth, F.; Friebel, S.; Rohde, A.; Giesecke, P.; Denschlag, D. Characteristics and attitudes of women in relation to chosen fertility preservation techniques: A prospective, multicenter questionnaire-based study with 144 participants. Eur. J. Obstet. Gynecol. Reprod. Biol. 2016, 201, 12–17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zanagnolo, V.; Sartori, E.; Trussardi, E.; Pasinetti, B.; Maggino, T. Preservation of ovarian function, reproductive ability and emotional attitudes in patients with malignant ovarian tumors. Eur. J. Obstet. Gynecol. Reprod. Biol. 2005, 123, 235–243. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Edge, B.; Holmes, D.; Makin, G. Sperm banking in adolescent cancer patients. Arch. Dis. Child. 2006, 91, 149–152. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Krouwel, E.M.; Jansen, T.G.; Nicolai, M.P.J.; Dieben, S.W.M.; Luelmo, S.A.C.; Putter, H.; Pelger, R.C.M.; Elzevier, H.W. Identifying the Need to Discuss Infertility Concerns Affecting Testicular Cancer Patients: An Evaluation (INDICATE Study). Cancers 2021, 13, 553. [Google Scholar] [CrossRef] [Scilit]
- Pacey, A.; Merrick, H.; Arden-Close, E.; Morris, K.; Rowe, R.; Stark, D.; Eiser, C. Implications of sperm banking for health-related quality of life up to 1 year after cancer diagnosis. Br. J. Cancer 2013, 108, 1004–1011. [Google Scholar] [CrossRef] [Scilit]
- Perez, S.; Lambert, S.D.; Lee, V.; Loiselle, C.G.; Chan, P.; Gupta, A.; Lo, K.; Rosberger, Z.; Zelkowitz, P. A fertility needs assessment survey of male cancer patients. Psychooncology 2018, 27, 2747–2753. [Google Scholar] [CrossRef] [Scilit]
- Schover, L.R.; Brey, K.; Lichtin, A.; Lipshultz, L.I.; Jeha, S. Knowledge and experience regarding cancer, infertility, and sperm banking in younger male survivors. J. Clin. Oncol. 2002, 20, 1880–1889. [Google Scholar] [CrossRef] [Scilit]
- Xi, W.; Gan, D.; Cuihua, S.; Peitao, W. A questionnaire survey on awareness of reproductive protection and autologous sperm preservation among cancer patients. J. Men’s Health 2020, 16, e19–e28. [Google Scholar] [CrossRef] [Scilit]
- Yee, S.; Fuller-Thomson, E.; Dwyer, C.; Greenblatt, E.; Shapiro, H. “Just what the doctor ordered”: Factors associated with oncology patients’ decision to bank sperm. Can. Urol. Assoc. J. 2012, 6, E174–E178. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, H.; Wang, G.; Cao, M.; Yin, L.; Xing, Y.; Wang, J.; Yang, J.; Zhang, J. Level of Knowledge and Needs on Fertility Preservation in Reproductive-Aged Male Patients with Cancer. J. Cancer Educ. 2020, 35, 321–326. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kayiira, A.; Neda John, J.; Zaake, D.; Xiong, S.; Kambugu Balagadde, J.; Gomez-Lobo, V.; Wabinga, H.; Ghebre, R. Understanding Fertility Attitudes and Outcomes Among Survivors of Adolescent and Young Adult Cancers in a Low-Resource Setting: A Registry-Based Computer-Assisted Telephone Interview Survey. J. Adolesc. Young Adult Oncol. 2023, 12, 520–528. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Marino, J.L.; Peate, M.; McNeil, R.; Orme, L.M.; McCarthy, M.C.; Glackin, A.; Sawyer, S.M. Experiences of Family and Partner Support in Fertility Decision-Making among Adolescents and Young Adults with Cancer: A National Australian Study. J. Adolesc. Young Adult Oncol. 2023; ahead of print. [CrossRef] [Scilit]
- Schlossman, J.; Vu, M.; Samborski, A.; Breit, K.; Thevenet-Morrison, K.; Wilbur, M. Identifying barriers individuals face in accessing fertility care after a gynecologic cancer diagnosis. Gynecol. Oncol. Rep. 2023, 49, 6. [Google Scholar]
- Vogt, K.S.; Hughes, J.; Wilkinson, A.; Mahmoodi, N.; Skull, J.; Wood, H.; McDougall, S.; Slade, P.; Greenfield, D.M.; Pacey, A.; et al. Preserving fertility in women with cancer (PreFer): Decision-making and patient-reported outcomes in women offered egg and embryo freezing prior to cancer treatment. Psychooncology 2018, 27, 2725–2732. [Google Scholar] [CrossRef] [Scilit]
- Ehrbar, V.; Scherzinger, L.; Urech, C.; Rochlitz, C.; Tschudin, S.; Sartorius, G. Fertility preservation in male cancer patients: A mixed methods assessment of experiences and needs. Urol. Oncol. 2022, 40, 385.e319–385.e325. [Google Scholar] [CrossRef] [Scilit]
- Ussher, J.M.; Parton, C.; Perz, J. Need for information, honesty and respect: Patient perspectives on health care professionals communication about cancer and fertility. Reprod. Health 2018, 15, 2. [Google Scholar] [CrossRef] [Scilit]
- Crawshaw, M.; Glaser, A.; Hale, J.; Sloper, P. Professionals’ view on the issues and challenges arising from providing a fertility preservations service sperm banking to teenage males with cancer. Hum. Fertil. 2004, 7, 23–30. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taylor, J.F.; Ott, M.A. Fertility Preservation after a Cancer Diagnosis: A Systematic Review of Adolescents’, Parents’, and Providers’ Perspectives, Experiences, and Preferences. J. Pediatr. Adolesc. Gynecol. 2016, 29, 585–598. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daly, C.; Micic, S.; Facey, M.; Speller, B.; Yee, S.; Kennedy, E.D.; Corter, A.L.; Baxter, N.N. A review of factors affecting patient fertility preservation discussions & decision-making from the perspectives of patients and providers. Eur. J. Cancer Care 2019, 28, e12945. [Google Scholar]
- Linnane, S.; Quinn, A.; Riordan, A.; Dowling, M. Women’s fertility decision-making with a diagnosis of breast cancer: A qualitative evidence synthesis. Int. J. Nurs. Pract. 2022, 28, e13036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Clasen, N.H.Z.; van der Perk, M.E.M.; Neggers, S.; Bos, A.M.E.; van den Heuvel-Eibrink, M.M. Experiences of Female Childhood Cancer Patients and Survivors Regarding Information and Counselling on Gonadotoxicity Risk and Fertility Preservation at Diagnosis: A Systematic Review. Cancers 2023, 15, 1946. [Google Scholar] [CrossRef] [Scilit]
- Goncalves, V.; Ferreira, P.L.; Saleh, M.; Tamargo, C.; Quinn, G.P. Perspectives of Young Women With Gynecologic Cancers on Fertility and Fertility Preservation: A Systematic Review. Oncologist 2022, 27, E251–E264. [Google Scholar] [CrossRef] [Scilit]
- Macklon, K.T.; Cjm Fauser, B. The female post-cancer fertility-counselling clinic: Looking beyond the freezer. A much needed addition to oncofertility care. Reprod. Biomed. Online 2019, 39, 179–181. [Google Scholar] [CrossRef] [Scilit]
- Salonia, A.; Capogrosso, P.; Castiglione, F.; Russo, A.; Gallina, A.; Ferrari, M.; Clementi, M.C.; Castagna, G.; Briganti, A.; Cantiello, F.; et al. Sperm banking is of key importance in patients with prostate cancer. Fertil. Steril. 2013, 100, 367–372.e361. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).