


Abstract
Background/Objectives: Nutraceuticals, including short-chain fatty acids (SCFAs) and antioxidants (AOXs), are nutrient-derived bioactive compounds considered as potential treatments for metabolic-associated steatotic liver disease (MASLD). However, in vitro studies of their effects are limited by inconsistent experimental conditions, including differences in cell lines, methods of steatosis induction, and culture media, and by reliance on qualitative rather than quantitative assessments. Here, we systematically evaluate the anti-steatotic potential of eight commonly used nutraceuticals—three SCFAs (butyrate, acetate, and propionate) and five AOXs (resveratrol, curcumin, berberine, chlorogenic acid, and vitamin E)—using a standardized in vitro approach. Methods: Following a systematic literature review to identify common experimental conditions, we developed an assay to validate steatosis induction and quantified the effects of the nutraceuticals. For our studies we used the HepG2 liver cancer cell line and the Fa2N-4 immortalized hepatocyte cell line. Steatosis was modeled by stimulating cells with free fatty acids and fructose for 48 h. Nutraceuticals were added either concurrently with steatotic stimulation, to assess preventive effects, or after 24 h to assess therapeutic effects. Anti-steatotic drugs (resmetirom, semaglutide, obeticholic acid, and a DGAT2 inhibitor) were included as positive controls. Intracellular triglyceride levels were measured to quantify steatosis. Results: A systematic review of 46 studies revealed large differences in culture conditions, steatosis induction, and nutraceutical assessment. In our experiments, most nutraceuticals did not reduce intracellular triglycerides, with the exception of vitamin E. Surprisingly, butyrate, berberine, and curcumin increased triglyceride accumulation. Resmetirom was the only drug that significantly decreased triglycerides, while obeticholic acid, semaglutide, and the DGAT2 inhibitor showed minimal or inconsistent effects. Fa2N-4 cells were generally more sensitive than HepG2 cells, showing larger absolute changes in triglyceride levels in response to both nutraceuticals and resmetirom. Conclusions: We established a standardized in vitro assay to evaluate the anti-steatotic potential of nutraceuticals. Using this system, we found that SCFAs and AOXs did not consistently reduce intracellular triglycerides, highlighting the need for quantitative assessments and careful validation when studying anti-steatotic interventions in vitro.
1. Introduction
Metabolic dysfunction-associated steatotic liver disease (MASLD) is the most prevalent chronic liver disease, affecting nearly 40% of the global population [1]. MASLD encompasses a spectrum of liver conditions, ranging from simple hepatic steatosis (fat accumulation) to metabolic-associated steatohepatitis (MASH), which can progress to fibrosis, cirrhosis, hepatocellular carcinoma, and end-stage liver disease. Extrahepatic features include insulin resistance, abdominal obesity, atherogenic dyslipidemia, and hypertension [2]. The pathogenesis of MASLD involves multiple metabolic disturbances, including excessive lipid influx from high-calorie diets, insulin resistance-driven adipose lipolysis, and increased de novo lipogenesis. Impaired fatty acid oxidation and export, mitochondrial dysfunction, and endoplasmic reticulum stress further exacerbate hepatic steatosis [3]. Lifestyle factors such as diet and physical activity influence disease onset, while genetic predisposition and gut microbiota dysbiosis modulate disease severity [4,5,6].
Although pharmacological interventions have recently emerged, US FDA-approved therapies remain limited. Resmetirom received conditional approval for treatment of MASH in 2024, followed by semaglutide in 2025 [7,8,9]. However, the response rates are modest (29.9% for resmetirom, 59% for semaglutide) [10,11]. Therefore, dietary interventions focusing on reducing caloric intake from high-fat and high-carbohydrate sources remain the first-line treatment [6]. In addition, functional dietary components, or ‘nutraceuticals,’ may offer targeted strategies for MASLD and early MASH. Nutraceuticals are bioactive molecules derived from food and include nutrients, herbal compounds, and phytochemicals [12,13]. Common examples are short-chain fatty acids (SCFAs), vitamin E, and phenolic acids such as curcumin and chlorogenic acid.
SCFAs are fatty acids with fewer than six carbon atoms, including acetate (C2), propionate (C3), and butyrate (C4), produced by intestinal microbiota through dietary fiber fermentation. SCFAs have been shown to improve hepatic steatosis in in vitro and preclinical models. For instance, butyrate reduced triglyceride accumulation in an in vitro gut-liver chip model using HepG2 and Caco-2 cells [14], and SCFAs improved metabolic function, restored gut barrier integrity, and regulated satiety in rodent models [15,16]. Mechanistically, SCFAs modulate lipid metabolism via PPAR-dependent shifts from lipogenesis to fatty acid oxidation, influencing SREBP-1c, PPARα, and CPT1A-AMPKα1-ACC pathways, and they may also act through histone deacetylase (HDAC) inhibition [14,17,18,19]. Animal studies suggest that the liver is a critical target for the effect of butyrate, as butyrate’s anti-steatotic effect was absent in mice that lacked hepatic PPARγ [17]. Clinical trials, however, could not demonstrate a causal improvement in hepatic steatosis following SCFA supplementation [20,21].
Phytochemicals, including polyphenols such as resveratrol, curcumin, berberine, chlorogenic acid, and vitamin E, are recognized for their antioxidant properties. They can protect hepatocytes from oxidative stress induced by lipid accumulation and exhibit anti-steatotic and anti-inflammatory effects in animal models and cell lines [21,22,23]. Vitamin E is currently the only phytochemical recommended off-label for MASLD patients without diabetes [21,24], although the evidence for its efficacy in improving steatohepatitis and fibrosis is limited and hepatotoxicity has been reported [25,26,27].
The aforementioned nutraceuticals and their main functions as well as protective (molecular) mechanisms in the context of MASLD are summarized in Table 1.
Table 1.
Overview of the literature on selected nutraceuticals that improve metabolic diseases and show mechanisms of protection in MASLD.
Recently, pharmaceutical interventions such as obeticholic acid, resmetirom, and semaglutide have gained attention (Table 2). While obeticholic acid was rejected for the treatment of MASH due to uncertain histopathological benefits versus risks [66,67,68], resmetirom and semaglutide have been approved [8,9]. Additionally, emerging compounds targeting hepatic triglyceride synthesis, including DGAT2 inhibitors, are under preclinical investigation [69,70,71].
Table 2.
Pharmaceutical drugs investigated in the context of MASLD. FXR, Farnesoid X receptor; GLP-1, glucagon-like peptide 1; THRB, thyroid hormone beta receptor; DGAT2, diacylglycerol O-acyltransferase 2.
Despite extensive mechanistic studies (Table 1), robust evidence demonstrating that nutraceuticals can reduce or reverse hepatic steatosis in terms of lipid accumulation is lacking. A major barrier is the absence of a standardized in vitro model to test anti-steatotic effects. Many studies investigate the anti-steatotic potential of nutraceuticals, yet all studies use different lipid/fructose stimulation, differ in stimulation duration, treatment duration and timing, and they do not always assess steatosis with a quantitative endpoint, such as absolute triglyceride levels. There has not been a standardized approach defined to assess the quantitative anti-steatotic effects of various nutraceuticals.
In this study, we defined such a model through a systematic review of cell-based studies on nutraceuticals in steatosis. We then used this assay to assess the anti-steatotic properties of SCFAs (butyrate, acetate, and propionate) and polyphenolic antioxidants (resveratrol, berberine, curcumin, chlorogenic acid, and vitamin E). Using the most reported conditions from the literature, we quantitatively measured intracellular triglycerides in two hepatocyte cell lines: tumor-derived HepG2 cells and immortalized hepatocyte-derived Fa2N-4 cells. Based on our literature review, we aim to standardize anti-steatotic cell line-based screening, from steatotic induction to pharmacological intervention, to improve the reliability of in vitro therapeutic investigations for MASLD.
2. Materials and Methods
2.1. Chemicals
To assess the potential anti-steatotic potency of nutraceuticals, chemicals were obtained from Sigma Aldrich (Merck KGaA, Darmstadt, Germany). SCFAs used in this study include sodium butyrate (catalog #303410), sodium acetate (catalog #S8750), and sodium propionate (catalog #P1880). Sodium chloride (catalog #106.404) was used as the vehicle control. The following plant-derived nutraceuticals were used: resveratrol (catalog #554325), curcumin (catalog #C7727), berberine (catalog #B3412), chlorogenic acid (catalog #C3878), and (±)-α-Tocopherol (vitamin E) solution (catalog #V-020).
2.2. Cell Culture
To study intracellular hepatocyte effects, HepG2 cells were obtained from ATCC (catalog #HB-8065, Manassas, VA, USA) and cultured in Dulbecco’s Modified Eagle’s Medium (DMEM) with GlutaMAX (catalog #10569010, Thermo Fisher Scientific, Waltham, MA, USA) containing 25 mM of glucose and supplemented with 10% heat-inactivated fetal bovine serum (FBS) (catalog #A5256701, Gibco, Thermo Fisher Scientific) and 1% penicillin-streptomycin (catalog #15140122, Thermo Fisher Scientific). Fa2N-4 cells [79] were obtained via Tebubio (catalog #IFH15, Tebubio, Le Perray-en-Yvelines, France) and cultured on coated plates with 0.02 mg/mL rat tail collagen-I (catalog #354249, Corning, New York, NY, USA) in Williams E medium with GlutaMAX (catalog #32551087, Gibco, Thermo Fisher Scientific) containing 11 mM glucose and supplemented with 10% heat-inactivated FBS (catalog #A5256701, Gibco, Thermo Fisher Scientific), 1% penicillin-streptomycin (catalog #15140122, Thermo Fisher Scientific), 20 mU/mL insulin (100 U/mL injection vial, Sanofi, Paris, France) and 100 nM dexamethasone (20 mg/mL stock, catalog #9265331, Centrafarm, Breda, The Netherlands). For experiments, cells were seeded in 24-well plates at a density of 105,000 cells per cm2 and left overnight to attach. Both cell lines were confirmed to be authentic and not cross-contaminated with other cell lines using short-tandem repeat profiling (Eurofins, Luxembourg City, Luxembourg).
To mimic hepatic steatosis in vitro, cells with a confluency of 60–70% were stimulated with culture media supplemented with 1 mM fructose (D-(−)-Fructose, F0127, Sigma, Merck KGaA) and a mixture of free fatty acids (FFA), palmitic acid, and oleic acid (catalog #03880 and P9767, Sigma Aldrich, Merck KGaA) in a 1:2 ratio for 24 h or 48 h. A total of 10 mM palmitic acid or oleic acid was dissolved in 100% EtOH, dried under gaseous N2, and dissolved in 10% bovine serum albumin (BSA) (catalog #A6003, Sigma, Merck KGaA) (pH adjusted to 7.4). BSA was used as a vehicle control. Cells were stimulated with 600 µM FFAs for 24 h unless otherwise specified.
2.3. Nutraceuticals and Pharmaceuticals
To measure the influence of various compounds on intracellular triglyceride levels, steatotic cells were stimulated with nutraceuticals or pharmaceuticals. The treatment approach was either at the same time as steatotic stimuli for 48 h (‘co-stimulation’, prevention) or after 24 h of steatotic stimuli exposure (‘post-stimulation’, intervention) (Table 2). Concentrations of nutraceuticals were based on consensus in Appendix A and cellular toxicity, relevant human blood levels, and drug ADME (absorption, distribution, metabolism, and excretion), including bioavailability (Appendix B). For pharmaceuticals, we used literature references, indicated in Table 3 below, previously cited to have at least 60% cell viability in HepG2 cells.
Table 3.
Therapeutics, solvents, and concentrations.
2.4. Triglyceride Quantification
To quantify intracellular triglycerides, we collected cell lysates. Briefly, cells were washed twice with 1x phosphate-buffered saline (PBS) (catalog #14190-169, Thermo Scientific) and collected in 1x Tris-buffered saline (TBS; home-made) to quantify intracellular triglycerides. Cells were lysed by sonication for 10 s at 40% amplitude. Prior to fat isolation, protein levels were measured using the Bicinchoninic Acid kit (BCATM Protein Assay Kit, catalog #23227, Pierce, Thermo Fisher Scientific) [82], and the sample input for fat isolation was equalized to the sample with the lowest protein concentration.
Lipids were extracted according to the Bligh and Dyer lipid extraction [83]. In short, chloroform/methanol (2:1) was used to separate lipids by vortexing and centrifugation of the samples. Samples were dried under a N2 flow, dissolved in 2% Triton in chloroform, vortexed, and left to dry. Next, samples were dissolved in demi water and incubated for one hour at 37 °C. The concentration of triglycerides was measured by an enzymatic colorimetric Triglycerides FS (catalog #157109910917, Diasys Diagnostic Systems GmbH, Holzheim, Germany) assay and normalized to protein. Precimat glycerol (catalog #10166588, Roche Diagnostics GmbH, Mannheim, Germany) was used as a reference (0.82–105 µM/mL) to make a standard curve and interpolate our samples.
2.5. Literature Review
To assess the existing literature, we conducted a literature search to identify relevant studies on nutraceuticals and their anti-steatotic effects. The search was performed using electronic databases including PubMed and Google Scholar. Keywords used included combinations of: “[nutraceutical] AND “steatosis”, “[nutraceutical] AND cell culture”, and “[nutraceutical] AND in vitro”. The nutraceuticals searched were: “butyrate”, “acetate”, “propionate”, “resveratrol”, “curcumin”, “berberine”, “chlorogenic acid”, and “vitamin E”. No formal search protocol or PRISMA guidelines were followed, as this review was exploratory in nature. Our selection criteria included the use of human in vitro hepatocyte cell lines in the published data, and only original research papers were included.
We included 46 independent studies, including some that explored multiple nutraceuticals. Therefore, 55 entries are reported, with each compound listed separately. We extracted information on the cell lines used, the media, the screening methodology, and the readouts. As no quantitative meta-analysis was performed, this review is subject to bias and may not comprehensively cover all relevant studies. The aim was to provide a broad overview rather than an exhaustive analysis.
2.6. Statistical Analysis
Statistical analyses were performed using BrightStat (Version 1.3.1, ‘https://secure.brightstat.com/index.php’ (accessed on 23 July 2025) [84]). Differences between groups with identical vehicles were tested using the unpaired Mann–Whitney U test (control versus treated) or Kruskal–Wallis (for >2 conditions). All values are reported as the mean of ≥3 replicates. Values with p < 0.05 were considered significant. Data visualization was conducted using GraphPad Prism (Version 10.4.1 (532), San Diego, CA, USA).
3. Results
3.1. Systematic Review of Studies on Nutraceutical Effects in Hepatic Steatosis
To investigate the impact of nutraceuticals on hepatic steatosis, we conducted a systematic literature review and assessed the degree of consensus across studies. We analyzed 46 studies that reported on the anti-steatotic properties of nutraceuticals using human hepatocyte-derived cell lines (Appendix A). In total, we identified 55 experimental entries, as some studies evaluated multiple compounds. The studies were analyzed for variations in cell lines, culture conditions, steatosis induction, and nutraceutical treatment protocol (Figure 1A).
Figure 1.
Literature overview on conditions under which nutraceuticals are investigated in the context of hepatic steatosis in human hepatocyte cell lines. (A) Number of studies per included nutraceutical, (B) cell lines used, (C) culture media used, (D) glucose concentration in culture media used, (E) duration of steatotic stimulation, (F) stimulations used to mimic steatotic-like phenotype, (G) type of treatment with nutraceuticals per study, (H) incubation time under which the effect of nutraceutical groups were studied, (I) nutraceutical concentrations primarily studied in included studies and (J) assessment of steatosis by neutral lipids.
Most selected studies (51 out of 55) investigating nutraceutical effects employed two-dimensional hepatocyte cell lines, primarily the hepatoblastoma-derived HepG2 cell line (Figure 1B). The cancerous origin of the HepG2 cell line affects its metabolic capacity, as reflected by the downregulation of PPAR signaling and cytochrome P450 drug-metabolizing enzymes [85,86]. The choice of basal culture medium also varied considerably (Figure 1C). Among the reviewed studies, 76% (42 out of 55) used DMEM-based media with glucose concentrations ranging from 5.5 mM to 25 mM (Figure 1D). However, most studies did not specify the exact DMEM formulation used. Experimental induction of steatosis varied widely across studies, using glucose, insulin, FFA, or combinations thereof (Figure 1E,F). Some studies additionally included serum starvation or glucose reduction steps before stimulation (Appendix A). Disease induction periods were generally short, typically 24 h, despite MASLD being a chronic condition (Figure 1E). The timing and duration of nutraceutical exposure also differed markedly, complicating comparisons between studies. Many studies applied nutraceuticals either concurrently with steatotic stimuli (“prevention” or “co-treated”) or after induction (“intervention” or “post-treated”) (see Appendix A and Figure 1G) for 24 h (Figure 1H). As reported concentrations varied substantially, we stratified studies by concentration range and highlighted the most effective concentration (‘*’) when multiple concentrations were used (Figure 1I and Appendix A). When compared with physiological concentrations (Appendix B), we used much higher concentrations than known human blood levels of these nutraceuticals, except for vitamin E [87]. While these concentrations are far below the reported half-maximal inhibitory concentration (IC50) [88], we must consider the difference in concentrations when interpreting the results.
We found ~75% of studies assessed steatosis qualitatively by immunohistochemical or immunofluorescent staining for neutral lipids or by biochemical quantification of intracellular triglycerides (Figure 1J). However, ~25% of studies reported anti-steatotic effects on transcriptional and/or protein level but did not quantify lipid accumulation (‘none’). Collectively, the wide variability in experimental design, including cell line selection, steatosis induction, and treatment conditions, precludes direct comparison and limits the interpretability of published findings regarding nutraceutical efficacy.
3.2. Development of a Standardized in Vitro Assay to Evaluate Anti-Steatotic Effects of Nutraceuticals
To address these inconsistencies across studies, we developed a standardized in vitro assay to evaluate the anti-steatotic effects of nutraceuticals. For this, we selected two cell lines. The HepG2 cancer-derived cell line was chosen because this is the most common cell line used (51 out of 55 studies, Figure 1B). In addition, we selected the Fa2N-4 cell line, which represents an immortalized hepatocyte line derived from a healthy human liver [79,89]. Using these two hepatocyte cell lines, we tested the anti-steatotic effect of eight nutraceuticals (two concentrations for each nutraceutical) under both preventive and therapeutic conditions by assessing intracellular triglyceride accumulation.
Steatosis was induced in a dose-dependent manner by exposing HepG2 and Fa2N-4 cells to a 1:2 mixture of FFA (saturated palmitic acid—unsaturated oleic acid) and 1 mM fructose, which closely mimics dietary conditions and aligns with current consensus in the field [90,91]. Basal intracellular triglyceride levels were higher in HepG2 cells than in Fa2N-4 cells (110 nmol triglycerides/mg protein vs. 0.8 nmol triglycerides/mg protein, respectively) (Figure 2). Exposure to FFA + fructose increased triglyceride levels in both cell lines in a dose-dependent manner. For subsequent nutraceutical experiments, we selected a moderate dose of 600 μM FFA + fructose. At this concentration, triglyceride levels increased approximately threefold in HepG2 cells and 179-fold in Fa2N-4 cells. This intermediate fat accumulation provides a suitable range for analyzing both preventive and therapeutic effects, allowing detection of subtle increases or decreases in intracellular triglyceride content.
Figure 2.
Hepatocyte cell lines HepG2 and Fa2N-4 accumulate lipids. (A) HepG2 and (B) Fa2N-4 cells stimulated for 24 h with BSA-conjugated free fatty acids (oleic acid and palmitic acid in a 2:1 ratio) with 1 mM fructose. All conditions include n = 5 technical replicates. *** p ≤ 0.001.
3.3. Anti-Steatotic Effects of Pharmaceuticals
To validate our assay, we first assessed the preventive and therapeutic anti-steatotic effects of four pharmaceutical compounds: the US FDA-approved drugs resmetirom and semaglutide, a DGAT2 inhibitor (PF 06424439), and obeticholic acid [9,90,92,93]. For the preventive experiments, both cell lines were treated with each compound for 48 h simultaneously with FFA and fructose stimuli. For the therapeutic (intervention) experiments, cells were first exposed to FFA and fructose for 24 h, then treated with the pharmaceuticals for an additional 24 h (Figure 3). In each experiment, compounds were tested at two concentrations.
Figure 3.
Changes in intracellular triglyceride levels in response to prevention or intervention drug treatment. (A) HepG2 cells treated with free fatty acids (FFA) and fructose together with pharmaceuticals at varying concentrations for 48 h as a preventive treatment strategy. (B) HepG2 cells treated with FFA and fructose for 24 h, after which pharmaceuticals at varying concentrations are added for another 24 h as an interventive treatment strategy. (C) Fa2N-4 cells treated with FFA and fructose, and preventive with pharmaceuticals. (D) Fa2N-4 cells treated with FFA and fructose, and intervented with pharmaceuticals. All experiments include n ≥ 3 technical replicates. * p ≤ 0.05.
Resmetirom consistently reduced intracellular triglycerides in both preventive and therapeutic experiments across both cell lines. Notably, its therapeutic effect was stronger in Fa2N-4 cells than in HepG2 cells. At a high concentration, resmetirom reduced intracellular triglyceride levels in Fa2N-4 cells by 3.5-fold in the preventive experiment (p = 0.05, Figure 3B), compared with only a 1.4-fold reduction in HepG2 cells (p = 0.05, Figure 3A). The other pharmaceuticals showed more variable effects depending on the concentration and treatment approach. For example, the DGAT2 inhibitor slightly reduced triglycerides in HepG2 cells at a low concentration (1.3-fold reduction, p = 0.05, Figure 3A), while obeticholic acid had a modest protective effect in Fa2N-4 cells at a high concentration (1.1-fold reduction, p = 0.046, Figure 3C). However, results were sometimes inconsistent or even contradictory. For instance, a high concentration of the DGAT2 inhibitor increased triglyceride levels in Fa2N-4 cells (1.2-fold, p = 0.05, Figure 3C), whereas a low concentration reduced triglyceride levels in HepG2 cells (Figure 3A,B).
These findings indicate that the potential of these compounds for MASLD treatment is highly context-dependent. Nevertheless, the robust effects of resmetirom validate our cellular models and experimental setup, supporting their use for testing the anti-steatotic capacity of nutraceuticals of interest.
3.4. Anti-Steatotic Effects of Nutraceuticals
We next evaluated the preventive and therapeutic potential of various nutraceuticals using the same experimental setup. Contrary to previous reports suggesting a beneficial role of SCFAs in MASLD, none of the three SCFAs we tested exhibited preventive or therapeutic effects in either cell line, at low or high concentrations (Figure 4A–D). In fact, butyrate, acetate, and propionate all showed pro-steatotic effects under at least one condition. This was particularly pronounced for butyrate, which increased intracellular triglyceride levels in both the preventive (1.7- and 2.7-fold in HepG2 and Fa2N-4 cells, respectively) and therapeutic experiments (1.5-fold increase in Fa2N-4 cells).
Figure 4.
Changes in intracellular triglyceride levels in response to prevention or intervention treatment. (A,E) HepG2 cells were simultaneously treated with FFA stimuli and nutraceuticals for 48 h (prevention). (B,F) HepG2 cells were treated with FFA stimuli for 24 h, after which nutraceuticals were added for an additional 24 h (intervention). (C,G) Fa2N-4 cells were simultaneously treated with FFA stimuli and nutraceuticals for 48 h (prevention). (D,H) Fa2N-4 cells were treated FFA stimuli for 24 h after which nutraceuticals were added for an additional 24 h (intervention). Short-chain fatty acids were applied at 1 mM (low) and 5 mM (high) concentration. Polyphenolic antioxidants were applied at 10 μM (low) and 50 μM (high). All experiments include n ≥ 3 technical replicates. * p ≤ 0.05, ** p ≤ 0.01.
The effects of polyphenolic AOXs on triglyceride accumulation were variable, depending on the compound, concentration, and treatment method. No therapeutic effects were observed for any of the polyphenols (Figure 4E–H). Vitamin E demonstrated a modest protective effect in HepG2 cells at a high concentration (1.2-fold decrease, p = 0.05, Figure 4E) and in Fa2N-4 cells at a low concentration (1.04-fold decrease, p = 0.05, Figure 4G), but had no effect under other conditions. Similarly, low concentrations of chlorogenic acid reduced triglycerides in Fa2N-4 cells by 1.04-fold (p = 0.05, Figure 4G).
Resveratrol produced contradictory results. In the preventive experiment, it decreased triglycerides by 1.04-fold in Fa2N-4 cells at a low concentration (p = 0.05, Figure 4G), but increased triglycerides by 1.2-fold in HepG2 cells at a high concentration (p = 0.05, Figure 4E). In contrast, berberine and curcumin consistently exhibited pro-steatotic effects in multiple conditions, with berberine increasing triglycerides 1.2- to 1.8-fold at high concentrations (except Fa2N-4 intervention, p = 0.513) and curcumin causing a 1.2- to 1.4-fold increase in preventive treatments (p = 0.05, Figure 4E,G).
Overall, we observed conflicting effects of nutraceuticals on intracellular triglycerides. All the SCFAs, including butyrate, increased triglyceride levels when used as a preventive treatment. Polyphenolic AOX compounds such as berberine and curcumin were surprisingly pro-steatotic under preventive conditions in both cell lines. Vitamin E showed the most consistent protective potential, but at different concentrations in the two cell lines (at a high concentration in HepG2 cells and at a low concentration in Fa2N-4 cells). Together, these findings emphasize that experimental variables such as cell lines and time of administration affect the anti-steatotic potential of nutraceuticals.
4. Discussion
To evaluate the anti-steatotic potential of nutraceuticals, standardized validation methods are essential, yet such standardization has been lacking in previous studies. To address this gap, we developed an in vitro assay to quantify intracellular triglyceride accumulation in two hepatocyte cell lines, HepG2 and Fa2N-4. Surprisingly, vitamin E, chlorogenic acid, and resveratrol induced only modest reductions in intracellular triglyceride levels in particular experimental conditions. In addition, several compounds—including SCFAs, berberine, and curcumin—elicited more pronounced pro-steatotic effects.
The pro-steatotic effects of SCFAs, particularly butyrate, contrast with results from the previous literature on in vivo rodents showing decreased liver triglycerides [17,29,94]. On the other hand, in vitro studies reported no change in intracellular triglycerides upon treatment with SCFAs, either in HepG2 cells [29] or in precision-cut liver slices from mice [95]. Previous studies have described SCFAs as anti-steatotic agents [28] or neutral in their effects on steatosis [29,95]. The pro-steatotic activity observed in our study may reflect intrinsic limitations of in vitro 2D cell lines, which lack physiological interactions with organs, particularly with the gut. Supporting this notion, co-culture models combining gut-derived Caco2 cells and HepG2 hepatocytes have shown that butyrate can reduce lipid accumulation [14]. As a mixture of enterocytes and colonocytes, Caco2 cells could metabolize up to 70–90% of butyrate, meaning fatty acid β oxidation metabolites, e.g., ATP and cAMP, could be the main effector molecules in the liver as opposed to whole butyrate, to stimulate the AMPK pathway [17,96].
Furthermore, in vivo, inter-organ crosstalk—such as enhanced adipose tissue lipolysis, an improved gut barrier, and modulation of satiety hormones—may further mitigate hepatic steatosis during butyrate supplementation [17,97,98], which could explain the absence of lipid reduction in our cell-based model. Hepatocytes take up SCFAs mainly by passive diffusion and to a lower extent by MCT1-mediated proton-coupled transport (SLC16A1) [99,100]. Intracellularly, SCFAs are converted to acetyl-CoA, which is a substrate for the citric acid cycle and a precursor for fatty acid synthesis [101]. However, under high-fat feeding, such as our in vitro condition, SCFAs can also be activated to acyl-CoAs, e.g., butyrate to butyryl-CoA, and subsequently be incorporated into triglycerides by esterification of diacylglyceride and butyryl-CoA by the enzyme DGAT1/2 [102]. Our applied concentration, derived from the literature, is much higher than physiological concentrations of SCFAs. Therefore, the administration of excessive SCFA concentrations may well explain our results of exacerbated lipid accumulation as a high-fat feeding state. Future investigation of lipogenesis markers such as DGAT activity and SREP1c protein levels would be needed to confirm this hypothesis.
In contrast to SCFAs, AOXs displayed variable effects on hepatic steatosis in our experiments, ranging from a mild decrease to no effect or even an increase in intracellular triglyceride content. We found a mildly significant decrease (1.04- to 1.2-fold change) in intracellular triglycerides for vitamin E in both cell lines; however, this was not consistent across the dosages, treatment strategies, or cell lines. Notably, both berberine and curcumin induced substantial triglyceride accumulation in HepG2 and Fa2N-4 cells—an observation not previously reported in the context of hepatic steatosis. Both were used at much higher concentrations than in vivo metabolically measured levels in human blood, whereas this was not the case for vitamin E, which was found to be in range [88]. Vitamin E may have exhibited other anti-steatotic or hepatoprotective effects including a reduction in serum aminotransferases, as reported in supplementation human trials [103]. The use of synthetic rather than natural AOX analogs may partly explain the limited anti-steatotic efficacy observed, consistent with a systematic review reporting 100% efficacy for natural AOXs compared to 87.7% for synthetic analogs in animal studies [104]. However, this factor alone does not account for the triglyceride accumulation induced by berberine and curcumin. Since our analysis was limited to intracellular triglyceride quantification, other potentially relevant mechanisms—such as alterations on gene expression levels in lipogenesis, lipolysis, fatty acid oxidation, and antioxidant activity remain unexamined in our study, yet explored in previous cited investigations [32,34,48,54,63,105]. Likewise, possible anti-inflammatory effects, such as secreted cytokines TNFα, IL1β and Il6 [57], gut barrier protection in terms of tight junction proteins [105], and anti-fibrotic effects by a reduction in ECM and collagen [65,95], were not assessed. Therefore, future investigations should aim to explore both the molecular mechanism of fatty acid oxidation and lipogenesis markers, oxidative, ER, and mitochondrial stress markers, while also measuring the consequences on intracellular triglycerides to conclude definitive anti-steatotic effects.
The pro-steatotic effects observed with both SCFAs and OAXs highlight both the relevance and the limitations of this study: anti-steatotic molecular mechanisms do not automatically translate into a reduction in triglyceride levels, but may even increase them. By utilizing a single-endpoint measurement, we can only speculate about the underlying mechanism by which these nutraceuticals increased intracellular triglyceride levels. The utilization of SCFAs as energy substrates is an obvious reason and thus the primary suspect, but for AOXs, berberine, and curcumin, this is not quite as directly deducible. In isolated mitochondria [106], curcumin has a dose-dependent uncoupling effect within the range that we tested the anti-steatotic effect of curcumin (10–50 µM), with mild uncoupling at 25 µM and more severe at 75–100 µM. As a result, there is reduced ATP availability, which may lead to inefficient fatty acid oxidation [106]. Similarly, berberine has also been found to induce oxidative stress by severe mitochondrial uncoupling as well as fragmentation in isolated mitochondria at different concentrations from 33.3, 66.7 and 133.3 ng/mL, similar to the concentrations we used [107]. Thus, AOXs at the concentrations that we used may have disturbed the mitochondria, leading to inadequate fatty acid oxidation.
We also observed that the experimental design, the treatment approach and the concentration of the treatment influenced the outcome. Preventive co-incubation of compounds with FFA and fructose resulted in more pronounced changes in lipid accumulation compared with shorter post-induction interventions in our study. Most nutrient-derived functional compounds are known for their preventive effects, while their intervention potential is currently still being investigated [108,109,110]. We also noticed that there was no specific trend depending on the concentration, except for a dose-dependent increase upon pro-steatotic effects. A different treatment concentration of the same compound may have differential effects, as a recent review on resveratrol noted a dual dose-dependent effect: a preventive, antioxidant effect at a lower dose, whereas intervention at a high dose had notable anti-cancerous properties [111]. In our case, we used resveratrol at a high concentration. It may therefore not have functioned to elevate oxidative stress resulting in lipid breakdown. To our knowledge, this is the first exploration that clearly distinguishes side-by-side the prevention vs. therapeutic effects of nutraceuticals solely based on triglyceride levels. We wish to highlight the importance of clearly defining treatment strategies in screening studies, as the literature rarely distinguishes between preventive and therapeutic setups, despite their potential impact on results.
To validate our assay, we included several pharmaceutical compounds—resmetirom, semaglutide, obeticholic acid, and a DGAT2 inhibitor. Resmetirom markedly reduced triglyceride levels in both HepG2 and Fa2N-4 cells. The other pharmaceutical agents induced only minor changes in intracellular triglycerides, suggesting that in vitro anti-steatotic effects are not easily captured in our simplified system, despite strong evidence from animal and clinical studies [10,73,93,112]. Semaglutide, a GLP-1 receptor agonist, primarily acts on the intestine, pancreas and brain, indirectly reducing hepatic steatosis through weight loss rather than direct hepatic mechanisms [11,76]. Nevertheless, we evaluated semaglutide in HepG2 and Fa2N-4 cells to determine whether it also elicits cell-autonomous effects on triglyceride handling, independent of its systemic actions. However, we did not observe anti-steatotic effects of resmetirom on isolated hepatocytes.
Obeticholic acid, a potent FXR agonist, acts directly on hepatocytes to modulate bile acid signaling and lipid metabolism. Obeticholic acid showed promise for treating nonalcoholic steatohepatitis, but it was recently rejected by both the US FDA and EMA due to adverse hepatic outcomes [66,113]. Despite its direct hepatic mechanism of action, we could not find a clear anti-steatotic effect in HepG2 and Fa2N-4 cells, which might be due to a lack of FXR signaling. Lastly, we tested a DGAT2 inhibitor (PF-06424439) and found that it did not change intracellular triglyceride levels in lipid-loaded hepatocytes. DGAT2 inhibitors target diacylglycerol O-acyltransferase 2, a key enzyme catalyzing the final step in triglyceride synthesis. Because DGAT2 acts directly within hepatocytes to regulate intracellular triglyceride production, these compounds are currently under clinical investigation as potential therapeutics for steatotic liver disease [78,93]. Specifically, PF-06424439 is still under preclinical investigation and shows slow, reversible, time-dependent inhibition of DGAT2 [114]. Previous reports on HepG2 [93] or primary hepatocytes from mice and primates [70] under steatotic stimuli only show an effective reduction in triglycerides upon dual inhibition of DGAT1 and DGAT2. DGAT1 may compensate for the absence or reduced activation of DGAT2 to synthesize triacylglycerol in human primary hepatocytes [115].
Differences in culture conditions can also cause variability across studies. Many reports do not specify basal media composition or glucose concentration, parameters that are critical for metabolic studies. For example, commonly used media contain supraphysiological glucose levels of 11 mM (e.g., Williams’ E, RPMI) or 25 mM (e.g., DMEM), compared to physiological plasma levels of 3.9–7.8 mM [116]. In our study, we maintained standard culture conditions to reproduce prior findings without altering glucose levels, serum content, or insulin supplementation. However, these factors likely influence the degree of steatosis induction and the apparent treatment response. Notably, the only publicly available formulation for Fa2N-4 cells, described by Padberg et al. (2021), includes insulin [117], which, combined with the different glucose concentrations between DMEM and Williams’ E medium, may have contributed to the unexpected pro-steatotic effects observed and the limited reproducibility across studies. Next, approximately 25% of reviewed studies reported no change in intracellular lipid accumulation, neither biochemically nor histologically. Given the potential for bias in qualitative lipid staining, we employed a quantitative whole-cell lipid extraction and intracellular triglyceride assay [118,119], which we consider a more objective and reproducible readout for assessing steatosis. Multiple previous nutraceutical studies reviewed do not show a change in neutral lipid levels despite anti-MASLD molecular adaptations [29,43,95]. However, we limited our investigation to a single-endpoint measurement and thus do not provide mechanistic insight into whether the nutraceuticals (or pharmaceuticals) affected lipid metabolism or other MASLD features such as oxidative stress and inflammation.
A key limitation of our study is the focus on a single endpoint—intracellular lipid content—in only two hepatocyte cell lines. It is possible that early anti-steatotic mechanisms, such as activation of fatty acid oxidation pathways (e.g., CPT1A–AMPKα1–ACC signaling), occurred without translating into measurable reductions in triglyceride levels. Additionally, we did not assess other MASLD-related processes, including oxidative stress, inflammation, or fibrosis. Including the investigation of molecular mechanisms and MASLD-related processes using a standardized assay in future studies will enhance our knowledge of the anti-steatotic effects of nutraceuticals.
5. Conclusions
Our findings underscore the importance of standardized assays in drug screening within disease-relevant models. The comparison of preventive and therapeutic in vitro treatment strategies revealed variable outcomes, emphasizing the need for further investigation in a standardized setting. Unexpectedly, several nutraceuticals previously reported as being anti-steatotic—butyrate, berberine, and curcumin—exhibited pro-steatotic effects in our hepatocyte models. These contradictory results highlight the critical need for transparency and reproducibility in in vitro research and may help explain the limited clinical success of certain nutraceutical interventions [108].
Finally, our study demonstrates the use of intracellular triglyceride quantification as a practical and informative endpoint for anti-steatotic compound screening. Establishing a clear in vitro anti-steatotic effect in hepatocytes should be considered a fundamental preclinical requirement before advancing candidates into clinical development. Incorporating this approach could strengthen the translational pipeline for nutrient-derived therapeutics targeting MASLD.
Author Contributions
Conceptualization, V.E.J.M.P., J.F., J.W.J. and J.A.H.; methodology, V.E.J.M.P. and J.A.H.; validation, V.E.J.M.P. and T.B.; formal analysis, V.E.J.M.P.; investigation, V.E.J.M.P.; resources, J.W.J. and J.F.; data curation, V.E.J.M.P.; writing—original draft preparation, V.E.J.M.P.; writing—review and editing, D.S. and J.A.H.; visualization, V.E.J.M.P.; supervision, D.S., J.A.H., S.W., J.F. and J.W.J.; project administration, V.E.J.M.P.; funding acquisition, J.W.J. and J.F. All authors have read and agreed to the published version of the manuscript.
Funding
V.E.J.M.P. received a PhD fellowship from the Graduate School of Medical Sciences, University of Groningen. S.W. is supported by the Netherlands Organ-on-Chip Initiative, a Netherlands Organization for Scientific Research (NWO) Gravitation project (024.003.001) funded by the Ministry of Education, Culture, and Science of the government of the Netherlands. J.W.J. is supported by NWO VICI grant 016.176.640. J.F. is supported by a European Research Council Consolidator grant (grant agreement No. 101001678), an NWO VICI grant (VI.C.202.022), an NWO KIC grant (KICH1.LWV04.21.013), the AMMODO Science Award 2023 for Biomedical Sciences from Stichting Ammodo, and the Dutch Heart Foundation AtheroNeth project.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in this study are included in the article. Further inquiries can be directed to the corresponding author.
Acknowledgments
The authors thank Kate Mc Intyre for editing the manuscript and Alfredo Wilson Rios-Ocampo and Roos Eilers for their technical support. During the preparation of this manuscript/study, the author(s) used Elicit (Elicit: The AI Research Assistant, https://elicit.com, accessed 26 October 2024) for the purpose of finding scientific research papers and Grammarly (2024, the Grammarly Handbook, https://www.grammarly.com/handbook/ (accessed on 18 December 2025)”.) for grammar and spelling checks. All authors have read and agreed to the published version of the manuscript.
Conflicts of Interest
The authors declare that they have no conflicts of interest. The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
Abbreviations
The following abbreviations are used in this manuscript:
| ACC | Acetyl-CoA carboxylase |
| AMPKα1 | AMP-activated catalytic subunit alpha 1 |
| AOXs | Antioxidants |
| CPT1A | Carnitine palmitoyltransferase I |
| DGAT2 | Diacylglycerol O-acyltransferase 2 |
| DMEM | Dulbecco’s modified eagle media |
| EMA | European Medicines Agency |
| FDA | Food and Drug Administration USA |
| FFA | Free fatty acids |
| HDAC | Histone deacetylase |
| MASH | Metabolically associated steatohepatitis |
| MASLD | Metabolically associated steatotic liver disease |
| PPARα | Peroxisome proliferator-activated receptor alpha |
| RPMI | Roswell Park Memorial Institute media |
| SCFAs | Short-chain fatty acids |
| SREBP-1c | Sterol regulatory element binding protein-1c |
Appendix A
Table A1.
Overview of in vitro data on the effects of various nutraceuticals in human hepatocytes. If multiple concentrations were used, * indicates the optimal condition per the authors. Abbreviations: 4-HNE, 4-hydroxynonenal; ACC, Acetyl-CoA Carboxylase; ALKBH5, AlkB Homolog 5 RNA Demethylase; ALT, Alanine Transaminase; AMPK, AMP-activated protein kinase; AST, Aspartate transaminase; BODIPY, 4,4-difluoro-4-bora-3a,4a-diaza-s-indacene; CCK-8, Cell Counting Kit-8; CPT, Carnitine Palmitoyltransferase; COL1A1, Collagen type I, alpha 1; DCF-DA, 2′,7′-dichlorodihydrofluorescein diacetate; FACS, Fluorescence-Activated Cell Sorting; FTO, FTO Alpha-Ketoglutarate Dependent Dioxygenase; JC-1, 5,5′,6,6′-Tetrachloro-1,1′,3,3′-tetraethylbenzimidazolylcarbocyanine iodide; MTT, 3-(4,5-dimethylthiazol-2-yl)-2,5-diphenyltetrazolium bromide; NAPDH, Nicotinamide adenine dinucleotide phosphate reduced; NRF2, Nuclear factor erythroid 2-related factor 2; PCR, Polymerase Chain Reaction; ROS, reactive oxygen species; SIRT1, Sirtuin-1; SOD, Superoxide dismutase; TMRE, Tetramethylrhodamine ethyl ester).
Appendix B
Table A2.
Relevant concentrations of short-chain fatty acids and antioxidant compounds. Summarized are the reported blood levels per compound based on the Human Metabolome Database (unless otherwise cited), the 50% inhibitory concentration (IC50) in liver cell lines reported in the ChEMBL database (unless otherwise cited), and the potential factors that influence bioavailability derived from DrugBank (unless otherwise cited).
References
- Wong, V.W.-S.; Ekstedt, M.; Wong, G.L.-H.; Hagström, H. Changing Epidemiology, Global Trends and Implications for Outcomes of NAFLD. J. Hepatol. 2023, 79, 842–852. [Google Scholar] [CrossRef] [Scilit]
- Targher, G.; Valenti, L.; Byrne, C.D. Metabolic Dysfunction–Associated Steatotic Liver Disease. N. Engl. J. Med. 2025, 393, 683–698. [Google Scholar] [CrossRef] [Scilit]
- Carli, F.; Della Pepa, G.; Sabatini, S.; Vidal Puig, A.; Gastaldelli, A. Lipid Metabolism in MASLD and MASH: From Mechanism to the Clinic. JHEP Rep. 2024, 6, 101185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kirpich, I.A.; Marsano, L.S.; McClain, C.J. Gut-Liver Axis, Nutrition, and Non-Alcoholic Fatty Liver Disease. Clin. Biochem. 2015, 48, 923–930. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shen, F.; Zheng, R.D.; Sun, X.Q.; Ding, W.J.; Wang, X.Y.; Fan, J.G. Gut Microbiota Dysbiosis in Patients with Non-Alcoholic Fatty Liver Disease. Hepatobiliary Pancreat. Dis. Int. 2017, 16, 375–381. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stefan, N.; Häring, H.U.; Cusi, K. Non-Alcoholic Fatty Liver Disease: Causes, Diagnosis, Cardiometabolic Consequences, and Treatment Strategies. Lancet Diabetes Endocrinol. 2019, 7, 313–324. [Google Scholar] [CrossRef] [Scilit]
- Dufour, J.F.; Anstee, Q.M.; Bugianesi, E.; Harrison, S.; Loomba, R.; Paradis, V.; Tilg, H.; Wong, V.W.S.; Zelber-Sagi, S. Current Therapies and New Developments in NASH. Gut 2022, 71, 2123–2134. [Google Scholar] [CrossRef] [Scilit]
- FDA. Approves First MASH Drug. Nat. Biotechnol. 2024, 42, 540. [Google Scholar] [CrossRef] [Scilit]
- Food and Drug Administration from U.S.A. FDA Approves Treatment for Serious Liver Disease Known as ‘MASH’|FDA. Available online: https://www-fda-gov.proxy-ub.rug.nl/drugs/news-events-human-drugs/fda-approves-treatment-serious-liver-disease-known-mash (accessed on 25 August 2025).
- Harrison, S.A.; Bedossa, P.; Guy, C.D.; Schattenberg, J.M.; Loomba, R.; Taub, R.; Labriola, D.; Moussa, S.E.; Neff, G.W.; Rinella, M.E.; et al. A Phase 3, Randomized, Controlled Trial of Resmetirom in NASH with Liver Fibrosis. New Engl. J. Med. 2024, 390, 497–509. [Google Scholar] [CrossRef] [Scilit]
- Newsome, P.N.; Buchholtz, K.; Cusi, K.; Linder, M.; Okanoue, T.; Ratziu, V.; Sanyal, A.J.; Sejling, A.-S.; Harrison, S.A. A Placebo-Controlled Trial of Subcutaneous Semaglutide in Nonalcoholic Steatohepatitis. New Engl. J. Med. 2021, 384, 1113–1124. [Google Scholar] [CrossRef] [Scilit]
- Nasri, H.; Baradaran, A.; Shirzad, H.; Kopaei, M.R. New Concepts in Nutraceuticals as Alternative for Pharmaceuticals. Int. J. Prev. Med. 2014, 5, 1487. [Google Scholar] [PubMed]
- Nwosu, O.K.; Ubaoji, K.I. Nutraceuticals: History, Classification and Market Demand. In Functional Foods and Nutraceuticals; Springer International Publishing: Cham, Switzerland, 2020; pp. 13–22. [Google Scholar] [CrossRef] [Scilit]
- Lee, S.Y.; Sung, J.H. Gut-Liver on a Chip toward an in Vitro Model of Hepatic Steatosis. Biotechnol. Bioeng. 2018, 115, 2817–2827. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tayyeb, J.Z.; Popeijus, H.E.; Mensink, R.P.; Konings, M.C.J.M.; Mulders, K.H.R.; Plat, J. The Effects of Short-chain Fatty Acids on the Transcription and Secretion of Apolipoprotein A-I in Human Hepatocytes in Vitro. J. Cell Biochem. 2019, 120, 17219. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Saleri, R.; Borghetti, P.; Ravanetti, F.; Cavalli, V.; Ferrari, L.; De Angelis, E.; Andrani, M.; Martelli, P. Effects of Different Short-Chain Fatty Acids (SCFA) on Gene Expression of Proteins Involved in Barrier Function in IPEC-J2. Porc. Health Manag. 2022, 8, 1–13. [Google Scholar] [CrossRef] [Scilit]
- Den Besten, G.; Bleeker, A.; Gerding, A.; Van Eunen, K.; Havinga, R.; Van Dijk, T.H.; Oosterveer, M.H.; Jonker, J.W.; Groen, A.K.; Reijngoud, D.J.; et al. Short-Chain Fatty Acids Protect Against High-Fat Diet-Induced Obesity via a PPARγ-Dependent Switch From Lipogenesis to Fat Oxidation. Diabetes 2015, 64, 2398–2408. [Google Scholar] [CrossRef] [Scilit]
- Waldecker, M.; Kautenburger, T.; Daumann, H.; Busch, C.; Schrenk, D. Inhibition of Histone-Deacetylase Activity by Short-Chain Fatty Acids and Some Polyphenol Metabolites Formed in the Colon. J. Nutr. Biochem. 2008, 19, 587–593. [Google Scholar] [CrossRef] [Scilit]
- Shimizu, H.; Masujima, Y.; Ushiroda, C.; Mizushima, R.; Taira, S.; Ohue-Kitano, R.; Kimura, I. Dietary Short-Chain Fatty Acid Intake Improves the Hepatic Metabolic Condition via FFAR3. Sci. Rep. 2019, 9, 16574. [Google Scholar] [CrossRef] [Scilit]
- Shi, A.; Li, T.; Zheng, Y.; Song, Y.; Wang, H.; Wang, N.; Dong, L.; Shi, H. Chlorogenic Acid Improves NAFLD by Regulating Gut Microbiota and GLP-1. Front. Pharmacol. 2021, 12, 693048. [Google Scholar] [CrossRef] [Scilit]
- Vadarlis, A.; Antza, C.; Bakaloudi, D.R.; Doundoulakis, I.; Kalopitas, G.; Samara, M.; Dardavessis, T.; Maris, T.; Chourdakis, M. Systematic Review with Meta-Analysis: The Effect of Vitamin E Supplementation in Adult Patients with Non-Alcoholic Fatty Liver Disease. J. Gastroenterol. Hepatol. 2021, 36, 311–319. [Google Scholar] [CrossRef] [Scilit]
- Rafiei, H.; Omidian, K.; Bandy, B. Dietary Polyphenols Protect Against Oleic Acid-Induced Steatosis in an in Vitro Model of NAFLD by Modulating Lipid Metabolism and Improving Mitochondrial Function. Nutrients 2019, 11, 541. [Google Scholar] [CrossRef] [Scilit]
- Hosseini, H.; Teimouri, M.; Shabani, M.; Koushki, M.; Babaei Khorzoughi, R.; Namvarjah, F.; Izadi, P.; Meshkani, R. Resveratrol Alleviates Non-Alcoholic Fatty Liver Disease through Epigenetic Modification of the Nrf2 Signaling Pathway. Int. J. Biochem. Cell Biol. 2020, 119, 105667. [Google Scholar] [CrossRef] [Scilit]
- Rinella, M.E.; Neuschwander-Tetri, B.A.; Siddiqui, M.S.; Abdelmalek, M.F.; Caldwell, S.; Barb, D.; Kleiner, D.E.; Loomba, R. AASLD Practice Guidance on the Clinical Assessment and Management of Nonalcoholic Fatty Liver Disease. Hepatology 2023, 77, 1797–1835. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bailey, R.L. Current Regulatory Guidelines and Resources to Support Research of Dietary Supplements in the United States. Crit. Rev. Food Sci. Nutr. 2020, 60, 298–309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, S.; Zhao, J.; Xie, F.; He, H.; Johnston, L.J.; Dai, X.; Wu, C.; Ma, X. Dietary Fiber-Derived Short-Chain Fatty Acids: A Potential Therapeutic Target to Alleviate Obesity-Related Nonalcoholic Fatty Liver Disease. Obes. Rev. 2021, 22, e13316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mitrović, M.; Stanković Popović, V.; Erceg, S.; Perišić Mitrović, M.; Dobrosavljević, A.; Stupar, A.; Vuković, P.; Zlatković, D.; Svorcan, P. Exploring the Potential of Oral Butyrate Supplementation in Metabolic Dysfunction-Associated Steatotic Liver Disease: Subgroup Insights from an Interventional Study. Int. J. Mol. Sci. 2025, 26, 5561. [Google Scholar] [CrossRef] [Scilit]
- Zhao, Z.H.; Wang, Z.X.; Zhou, D.; Han, Y.; Ma, F.; Hu, Z.; Xin, F.Z.; Liu, X.L.; Ren, T.Y.; Zhang, F.; et al. Sodium Butyrate Supplementation Inhibits Hepatic Steatosis by Stimulating Liver Kinase B1 and Insulin-Induced Gene. Cell. Mol. Gastroenterol. Hepatol. 2021, 12, 857–871. [Google Scholar] [CrossRef] [Scilit]
- Zhou, D.; Chen, Y.W.; Zhao, Z.H.; Yang, R.X.; Xin, F.Z.; Liu, X.L.; Pan, Q.; Zhou, H.; Fan, J.G. Sodium Butyrate Reduces High-Fat Diet-Induced Non-Alcoholic Steatohepatitis through Upregulation of Hepatic GLP-1R Expression. Exp. Mol. Med. 2018, 50, 1–12. [Google Scholar] [CrossRef] [Scilit]
- Cook, K.J.; Coulter, A.; Keenan, M.; Greenway, F.; Losso, J.N. Sodium Propionate or Sodium Butyrate Promotes Fatty Acid Oxidation in HepG2 Cells Under Oxidative Stress. J. Med. Food 2023, 26, 74–79. [Google Scholar] [CrossRef] [Scilit]
- Pirozzi, C.; Lama, A.; Annunziata, C.; Cavaliere, G.; De Caro, C.; Citraro, R.; Russo, E.; Tallarico, M.; Iannone, M.; Ferrante, M.C.; et al. Butyrate Prevents Valproate-Induced Liver Injury: In Vitro and in Vivo Evidence. FASEB J. 2020, 34, 676–690. [Google Scholar] [CrossRef] [Scilit]
- Song, Q.; Zhang, X.; Liu, W.; Wei, H.; Liang, W.; Zhou, Y.; Ding, Y.; Ji, F.; Ho-Kwan Cheung, A.; Wong, N.; et al. Bifidobacterium Pseudolongum-Generated Acetate Suppresses Non-Alcoholic Fatty Liver Disease-Associated Hepatocellular Carcinoma. J. Hepatol. 2023, 79, 1352–1365. [Google Scholar] [CrossRef] [Scilit]
- Salehi, B.; Mishra, A.P.; Nigam, M.; Sener, B.; Kilic, M.; Sharifi-Rad, M.; Fokou, P.V.T.; Martins, N.; Sharifi-Rad, J. Resveratrol: A Double-Edged Sword in Health Benefits. Biomedicines 2018, 6, 91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wan, S.; Zhang, L.; Quan, Y.; Wei, K. Resveratrol-Loaded PLGA Nanoparticles: Enhanced Stability, Solubility and Bioactivity of Resveratrol for Non-Alcoholic Fatty Liver Disease Therapy. R. Soc. Open Sci. 2018, 5, 181457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, Y.; Chen, M.; Zhou, Y.; Yi, L.; Gao, Y.; Ran, L.; Chen, S.; Zhang, T.; Zhou, X.; Zou, D.; et al. Resveratrol Improves Hepatic Steatosis by Inducing Autophagy through the CAMP Signaling Pathway. Mol. Nutr. Food Res. 2015, 59, 1443–1457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, J.; Wang, P.; Cui, Y.; Hu, X.; Chen, F.; Ma, C. Alleviation Effects of Microbial Metabolites from Resveratrol on Non-Alcoholic Fatty Liver Disease. Foods 2023, 12, 94. [Google Scholar] [CrossRef] [Scilit]
- Zhou, R.; Yi, L.; Ye, X.; Zeng, X.; Liu, K.; Qin, Y.; Zhang, Q.; Mi, M. Resveratrol Ameliorates Lipid Droplet Accumulation in Liver Through a SIRT1/ ATF6-Dependent Mechanism. Cell. Physiol. Biochem. 2018, 51, 2397–2420. [Google Scholar] [CrossRef] [Scilit]
- Izdebska, M.; Piątkowska-Chmiel, I.; Korolczuk, A.; Herbet, M.; Gawrońska-Grzywacz, M.; Gieroba, R.; Sysa, M.; Czajkowska-Bania, K.; Cygal, M.; Korga, A.; et al. The Beneficial Effects of Resveratrol on Steatosis and Mitochondrial Oxidative Stress in HepG2 Cells. Can. J. Physiol. Pharmacol. 2017, 95, 1442–1453. [Google Scholar] [CrossRef] [Scilit]
- Wang, G.L.; Fu, Y.C.; Xu, W.C.; Feng, Y.Q.; Fang, S.R.; Zhou, X.H. Resveratrol Inhibits the Expression of SREBP1 in Cell Model of Steatosis via Sirt1–FOXO1 Signaling Pathway. Biochem. Biophys. Res. Commun. 2009, 380, 644–649. [Google Scholar] [CrossRef] [Scilit]
- Tang, L.Y.; Chen, Y.; Rui, B.B.; Hu, C.M. Resveratrol Ameliorates Lipid Accumulation in HepG2 Cells, Associated with down-Regulation of Lipin1 Expression. Can. J. Physiol. Pharmacol. 2016, 94, 185–189. [Google Scholar] [CrossRef] [Scilit]
- Shang, J.; Chen, L.L.; Xiao, F.X.; Sun, H.; Ding, H.C.; Xiao, H. Resveratrol Improves Non-Alcoholic Fatty Liver Disease by Activating AMP-Activated Protein Kinase. Acta Pharmacol. Sin. 2008, 29, 698–706. [Google Scholar] [CrossRef] [Scilit]
- Hou, X.; Xu, S.; Maitland-Toolan, K.A.; Sato, K.; Jiang, B.; Ido, Y.; Lan, F.; Walsh, K.; Wierzbicki, M.; Verbeuren, T.J.; et al. SIRT1 Regulates Hepatocyte Lipid Metabolism through Activating AMP-Activated Protein Kinase. J. Biol. Chem. 2008, 283, 20015. [Google Scholar] [CrossRef] [Scilit]
- Rafiei, H.; Omidian, K.; Bandy, B. Comparison of Dietary Polyphenols for Protection against Molecular Mechanisms Underlying Nonalcoholic Fatty Liver Disease in a Cell Model of Steatosis. Mol. Nutr. Food Res. 2017, 61, 1600781. [Google Scholar] [CrossRef] [Scilit]
- Ardid-ruiz, A.; Ibars, M.; Mena, P.; Del Rio, D.; Muguerza, B.; Arola, L.; Aragonès, G.; Suárez, M. Resveratrol Treatment Enhances the Cellular Response to Leptin by Increasing OBRb Content in Palmitate-Induced Steatotic HepG2 Cells. Int. J. Mol. Sci. 2019, 20, 6282. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gupta, S.C.; Patchva, S.; Aggarwal, B.B. Therapeutic Roles of Curcumin: Lessons Learned from Clinical Trials. AAPS J. 2013, 15, 195–218. [Google Scholar] [CrossRef] [Scilit]
- Shan, D.; Wang, J.; Di, Q.; Jiang, Q.; Xu, Q. Steatosis Induced by Nonylphenol in HepG2 Cells and the Intervention Effect of Curcumin. Food Funct. 2022, 13, 327–343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pipitone, R.M.; Zito, R.; Lupo, G.; Javed, A.; La Mantia, C.; Di Maria, G.; Pratelli, G.; Di Salvo, F.; Fontana, S.; Pucci, M.; et al. Curcumin and Andrographolide Co-Administration Safely Prevent Steatosis Induction and ROS Production in HepG2 Cell Line. Molecules 2023, 28, 1261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, Q.; Liu, Y.; Wu, Y.; Chen, Y. Dihydrocurcumin Ameliorates the Lipid Accumulation, Oxidative Stress and Insulin Resistance in Oleic Acid-Induced L02 and HepG2 Cells. Biomed. Pharmacother. 2018, 103, 1327–1336. [Google Scholar] [CrossRef] [Scilit]
- Stellavato, A.; Pirozzi, A.V.A.; De Novellis, F.; Scognamiglio, I.; Vassallo, V.; Giori, A.M.; De Rosa, M.; Schiraldi, C. In Vitro Assessment of Nutraceutical Compounds and Novel Nutraceutical Formulations in a Liver-Steatosis-Based Model. Lipids Health Dis. 2018, 17, 24. [Google Scholar] [CrossRef] [Scilit]
- Li, S.; Ma, Y.; Chen, W. Active Ingredients of Erhuang Quzhi Granules for Treating Non-Alcoholic Fatty Liver Disease Based on the NF-ΚB/NLRP3 Pathway. Fitoterapia 2023, 171, 105704. [Google Scholar] [CrossRef] [Scilit]
- Song, D.; Hao, J.; Fan, D. Biological Properties and Clinical Applications of Berberine. Front. Med. 2020, 14, 564–582. [Google Scholar] [CrossRef] [Scilit]
- Yang, S.; Cao, S.; Li, C.; Zhang, J.; Liu, C.; Qiu, F.; Kang, N. Berberrubine, a Main Metabolite of Berberine, Alleviates Non-Alcoholic Fatty Liver Disease via Modulating Glucose and Lipid Metabolism and Restoring Gut Microbiota. Front. Pharmacol. 2022, 13, 913378. [Google Scholar] [CrossRef] [Scilit]
- Khorzoughi, R.B.; Namvarjah, F.; Teimouri, M.; Hosseini, H.; Meshkani, R. In-Vitro Synergistic Effect of Metformin and Berberine on High Glucose-Induced Lipogenesis. Iran. J. Pharm. Res. 2019, 18, 1921–1930. [Google Scholar] [CrossRef] [Scilit]
- Fan, H.; Chen, Y.Y.; Bei, W.J.; Wang, L.Y.; Chen, B.T.; Guo, J. In Vitro Screening for Antihepatic Steatosis Active Components within Coptidis Rhizoma Alkaloids Extract Using Liver Cell Extraction with HPLC Analysis and a Free Fatty Acid-Induced Hepatic Steatosis HepG2 Cell Assay. Evid.-Based Complement. Altern. Med. 2013, 2013, 459390. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kong, W.J.; Zhang, H.; Song, D.Q.; Xue, R.; Zhao, W.; Wei, J.; Wang, Y.M.; Shan, N.; Zhou, Z.X.; Yang, P.; et al. Berberine Reduces Insulin Resistance through Protein Kinase C-Dependent up-Regulation of Insulin Receptor Expression. Metabolism 2009, 58, 109–119. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Santana-Gálvez, J.; Cisneros-Zevallos, L.; Jacobo-Velázquez, D.A. Chlorogenic Acid: Recent Advances on Its Dual Role as a Food Additive and a Nutraceutical against Metabolic Syndrome. Mol. A J. Synth. Chem. Nat. Prod. Chem. 2017, 22, 358. [Google Scholar] [CrossRef] [Scilit]
- Tsukui, T.; Chen, Z.; Fuda, H.; Furukawa, T.; Oura, K.; Sakurai, T.; Hui, S.P.; Chiba, H. Novel Fluorescence-Based Method to Characterize the Antioxidative Effects of Food Metabolites on Lipid Droplets in Cultured Hepatocytes. J. Agric. Food Chem. 2019, 67, 9934–9941. [Google Scholar] [CrossRef] [Scilit]
- Namvarjah, F.; Shokri-Afra, H.; Moradi-Sardareh, H.; Khorzoughi, R.B.; Pasalar, P.; Panahi, G.; Meshkani, R. Chlorogenic Acid Improves Anti-Lipogenic Activity of Metformin by Positive Regulating of AMPK Signaling in HepG2 Cells. Cell Biochem. Biophys. 2022, 80, 537–545. [Google Scholar] [CrossRef] [Scilit]
- Ma, K.; Sheng, W.; Song, X.; Song, J.; Li, Y.; Huang, W.; Liu, Y. Chlorogenic Acid from Burdock Roots Ameliorates Oleic Acid-Induced Steatosis in HepG2 Cells through AMPK/ACC/CPT-1 Pathway. Molecules 2023, 28, 7257. [Google Scholar] [CrossRef] [Scilit]
- Hao, S.; Xiao, Y.; Lin, Y.; Mo, Z.; Chen, Y.; Peng, X.; Xiang, C.; Li, Y.; Li, W. Chlorogenic Acid-Enriched Extract from Eucommia Ulmoides Leaves Inhibits Hepatic Lipid Accumulation through Regulation of Cholesterol Metabolism in HepG2 Cells. Pharm. Biol. 2016, 54, 251–259. [Google Scholar] [CrossRef] [Scilit]
- Rebollo-Hernanz, M.; Aguilera, Y.; Martín-Cabrejas, M.A.; Gonzalez de Mejia, E. Activating Effects of the Bioactive Compounds From Coffee By-Products on FGF21 Signaling Modulate Hepatic Mitochondrial Bioenergetics and Energy Metabolism in Vitro. Front. Nutr. 2022, 9, 866233. [Google Scholar] [CrossRef] [Scilit]
- Nguyen, M.; Asgharpour, A.; Dixon, D.L.; Sanyal, A.J.; Mehta, A. Emerging Therapies for MASLD and Their Impact on Plasma Lipids. Am. J. Prev. Cardiol. 2024, 17, 100638. [Google Scholar] [CrossRef] [Scilit]
- Podszun, M.C.; Alawad, A.S.; Lingala, S.; Morris, N.; Huang, W.C.A.; Yang, S.; Schoenfeld, M.; Rolt, A.; Ouwerkerk, R.; Valdez, K.; et al. Vitamin E Treatment in NAFLD Patients Demonstrates That Oxidative Stress Drives Steatosis through Upregulation of De-Novo Lipogenesis. Redox Biol. 2020, 37, 101710. [Google Scholar] [CrossRef] [Scilit]
- Bartolini, D.; Torquato, P.; Barola, C.; Russo, A.; Rychlicki, C.; Giusepponi, D.; Bellezza, G.; Sidoni, A.; Galarini, R.; Svegliati-Baroni, G.; et al. Nonalcoholic Fatty Liver Disease Impairs the Cytochrome P-450-Dependent Metabolism of α-Tocopherol (Vitamin E). J. Nutr. Biochem. 2017, 47, 120–131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pingitore, P.; Sasidharan, K.; Ekstrand, M.; Prill, S.; Lindén, D.; Romeo, S. Human Multilineage 3D Spheroids as a Model of Liver Steatosis and Fibrosis. Int. J. Mol. Sci. 2019, 20, 1629. [Google Scholar] [CrossRef] [Scilit]
- FDA. Due to Risk of Serious Liver Injury, FDA Restricts Use of Ocaliva (Obeticholic Acid) in Primary Biliary Cholangitis (PBC) Patients with Advanced Cirrhosis; FDA: Silver Spring, MD, USA, 2024.
- Younossi, Z.M.; Ratziu, V.; Loomba, R.; Rinella, M.; Anstee, Q.M.; Goodman, Z.; Bedossa, P.; Geier, A.; Beckebaum, S.; Newsome, P.; et al. Obeticholic Acid for the Treatment of Non-Alcoholic Steatohepatitis: Interim Analysis from a Multicentre, Randomised, Placebo-Controlled Phase 3 Trial. Lancet 2019, 394, 2184–2196. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Singh, A.B.; Dong, B.; Kraemer, F.B.; Xu, Y.; Zhang, Y.; Liu, J. FXR Activation by Obeticholic Acid Elevates Liver LDL Receptor Expression by MRNA Stabilization and Reduces Plasma LDL-Cholesterol in Mice. Arterioscler. Thromb. Vasc. Biol. 2018, 38, 2448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nisticò, C.; Pagliari, F.; Chiarella, E.; Guerreiro, J.F.; Marafioti, M.G.; Aversa, I.; Genard, G.; Hanley, R.; Garcia-Calderón, D.; Bond, H.M.; et al. Lipid Droplet Biosynthesis Impairment through Dgat2 Inhibition Sensitizes Mcf7 Breast Cancer Cells to Radiation. Int. J. Mol. Sci. 2021, 22, 10102. [Google Scholar] [CrossRef] [Scilit]
- McLaren, D.G.; Han, S.; Murphy, B.A.; Wilsie, L.; Stout, S.J.; Zhou, H.; Roddy, T.P.; Gorski, J.N.; Metzger, D.E.; Shin, M.K.; et al. DGAT2 Inhibition Alters Aspects of Triglyceride Metabolism in Rodents but Not in Non-Human Primates. Cell Metab. 2018, 27, 1236–1248.e6. [Google Scholar] [CrossRef] [Scilit]
- Rong, S.; Xia, M.; Vale, G.; Wang, S.; Kim, C.W.; Li, S.; McDonald, J.G.; Radhakrishnan, A.; Horton, J.D. DGAT2 Inhibition Blocks SREBP-1 Cleavage and Improves Hepatic Steatosis by Increasing Phosphatidylethanolamine in the ER. Cell Metab. 2024, 36, 617. [Google Scholar] [CrossRef] [Scilit]
- Mullard, A. FDA Rejects NASH Drug. Nat. Rev. Drug Discov. 2020, 19, 501. [Google Scholar] [CrossRef] [Scilit]
- Neuschwander-Tetri, B.A.; Loomba, R.; Sanyal, A.J.; Lavine, J.E.; Van Natta, M.L.; Abdelmalek, M.F.; Chalasani, N.; Dasarathy, S.; Diehl, A.M.; Hameed, B.; et al. Farnesoid X Nuclear Receptor Ligand Obeticholic Acid for Non-Cirrhotic, Non-Alcoholic Steatohepatitis (FLINT): A Multicentre, Randomised, Placebo-Controlled Trial. Lancet 2015, 385, 956–965. [Google Scholar] [CrossRef] [Scilit]
- Ratziu, V.; Scanlan, T.S.; Bruinstroop, E. Thyroid Hormone Receptor-β Analogues for the Treatment of Metabolic Dysfunction-Associated Steatohepatitis (MASH). J. Hepatol. 2025, 82, 375–387. [Google Scholar] [CrossRef] [Scilit]
- Ezhilarasan, D. Mechanism of Semaglutide in MASLD Treatment: Where Is the Master Key? J. Gastroenterol. Hepatol. 2025, 40, 2163–2175. [Google Scholar] [CrossRef] [Scilit]
- Papakonstantinou, I.; Tsioufis, K.; Katsi, V. Spotlight on the Mechanism of Action of Semaglutide. Curr. Issues Mol. Biol. 2024, 46, 14514. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Futatsugi, K.; Kung, D.W.; Orr, S.T.M.; Cabral, S.; Hepworth, D.; Aspnes, G.; Bader, S.; Bian, J.; Boehm, M.; Carpino, P.A.; et al. Discovery and Optimization of Imidazopyridine-Based Inhibitors of Diacylglycerol Acyltransferase 2 (DGAT2). J. Med. Chem. 2015, 58, 7173–7185. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Amin, N.B.; Carvajal-Gonzalez, S.; Purkal, J.; Zhu, T.; Crowley, C.; Perez, S.; Chidsey, K.; Kim, A.M.; Goodwin, B. Targeting Diacylglycerol Acyltransferase 2 for the Treatment of Nonalcoholic Steatohepatitis. Sci. Transl. Med. 2019, 11, 9701. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hariparsad, N.; Carr, B.A.; Evers, R.; Chu, X. Comparison of Immortalized Fa2N-4 Cells and Human Hepatocytes as in Vitro Models for Cytochrome P450 Induction. Drug Metab. Dispos. 2008, 36, 1046–1055. [Google Scholar] [CrossRef] [Scilit]
- Wang, X.; Wang, L.; Geng, L.; Tanaka, N.; Ye, B. Resmetirom Ameliorates NASH-Model Mice by Suppressing STAT3 and NF-ΚB Signaling Pathways in an RGS5-Dependent Manner. Int. J. Mol. Sci. 2023, 24, 5843. [Google Scholar] [CrossRef] [Scilit]
- Qi, L.; Groeger, M.; Sharma, A.; Goswami, I.; Chen, E.; Zhong, F.; Ram, A.; Healy, K.; Hsiao, E.C.; Willenbring, H.; et al. Adipocyte Inflammation Is the Primary Driver of Hepatic Insulin Resistance in a Human IPSC-Based Microphysiological System. Nat. Commun. 2024, 15, 7991. [Google Scholar] [CrossRef] [Scilit]
- Smith, P.K.; Krohn, R.I.; Hermanson, G.T.; Mallia, A.K.; Gartner, F.H.; Provenzano, M.D.; Fujimoto, E.K.; Goeke, N.M.; Olson, B.J.; Klenk, D.C. Measurement of Protein Using Bicinchoninic Acid. Anal. Biochem. 1985, 150, 76–85. [Google Scholar] [CrossRef] [Scilit]
- Sündermann, A.; Eggers, L.F.; Schwudke, D. Liquid Extraction: Bligh and Dyer. In Encyclopedia of Lipidomics; Springer Netherlands: Dordrecht, The Netherlands, 2016; pp. 1–4. [Google Scholar]
- Stricker, D. BrightStat.Com: Free Statistics Online. Comput. Methods Programs Biomed. 2008, 92, 135–143. [Google Scholar] [CrossRef] [Scilit]
- Ramboer, E.; Vanhaecke, T.; Rogiers, V.; Vinken, M. Immortalized Human Hepatic Cell Lines for in Vitro Testing and Research Purposes. Methods Mol. Biol. 2015, 1250, 53. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smiriglia, A.; Lorito, N.; Serra, M.; Perra, A.; Morandi, A.; Kowalik, M.A. Sex Difference in Liver Diseases: How Preclinical Models Help to Dissect the Sex-Related Mechanisms Sustaining NAFLD and HCC. iScience 2023, 26, 108363. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wishart, D.S.; Guo, A.C.; Oler, E.; Wang, F.; Anjum, A.; Peters, H.; Dizon, R.; Sayeeda, Z.; Tian, S.; Lee, B.L.; et al. HMDB 5.0: The Human Metabolome Database for 2022. Nucleic Acids Res. 2022, 50, D622–D631. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zdrazil, B.; Felix, E.; Hunter, F.; Manners, E.J.; Blackshaw, J.; Corbett, S.; de Veij, M.; Ioannidis, H.; Lopez, D.M.; Mosquera, J.F.; et al. The ChEMBL Database in 2023: A Drug Discovery Platform Spanning Multiple Bioactivity Data Types and Time Periods. Nucleic Acids Res. 2024, 52, D1180. [Google Scholar] [CrossRef] [Scilit]
- Li, B.H.; He, F.P.; Yang, X.; Chen, Y.W.; Fan, J.G. Steatosis Induced CCL5 Contributes to Early-Stage Liver Fibrosis in Nonalcoholic Fatty Liver Disease Progress. Transl. Res. 2017, 180, 103–117.e4. [Google Scholar] [CrossRef] [Scilit]
- Gatzios, A.; Rombaut, M.; Buyl, K.; De Kock, J.; Rodrigues, R.M.; Rogiers, V.; Vanhaecke, T.; Boeckmans, J. From NAFLD to MAFLD: Aligning Translational In Vitro Research to Clinical Insights. Biomedicines 2022, 10, 161. [Google Scholar] [CrossRef] [Scilit]
- Zhang, X.; Lau, H.C.H.; Yu, J. Pharmacological Treatment for Metabolic Dysfunction–Associated Steatotic Liver Disease and Related Disorders: Current and Emerging Therapeutic Options. Pharmacol. Rev. 2025, 77, 100018. [Google Scholar] [CrossRef] [Scilit]
- Stefan, N.; Yki-Järvinen, H.; Neuschwander-Tetri, B.A. Metabolic Dysfunction-Associated Steatotic Liver Disease: Heterogeneous Pathomechanisms and Effectiveness of Metabolism-Based Treatment. Lancet Diabetes Endocrinol. 2025, 13, 134–148. [Google Scholar] [CrossRef] [Scilit]
- Longo, M.; Paolini, E.; Di Benedetto, P.; Tomassini, E.; Meroni, M.; Dongiovanni, P. DGAT1 and DGAT2 Inhibitors for Metabolic Dysfunction-Associated Steatotic Liver Disease (MASLD) Management: Benefits for Their Single or Combined Application. Int. J. Mol. Sci. 2024, 25, 9074. [Google Scholar] [CrossRef] [Scilit]
- Deng, M.; Qu, F.; Chen, L.; Liu, C.; Zhang, M.; Ren, F.; Guo, H.; Zhang, H.; Ge, S.; Wu, C.; et al. SCFAs Alleviated Steatosis and Inflammation in Mice with NASH Induced by MCD. J. Endocrinol. 2020, 245, 425–437. [Google Scholar] [CrossRef] [Scilit]
- Prins, G.H.; Rios-Morales, M.; Gerding, A.; Reijngoud, D.J.; Olinga, P.; Bakker, B.M. The Effects of Butyrate on Induced Metabolic-Associated Fatty Liver Disease in Precision-Cut Liver Slices. Nutrients 2021, 13, 4203. [Google Scholar] [CrossRef] [Scilit]
- Salvi, P.S.; Cowles, R.A. Butyrate and the Intestinal Epithelium: Modulation of Proliferation and Inflammation in Homeostasis and Disease. Cells 2021, 10, 1775. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Canfora, E.E.; Jocken, J.W.; Blaak, E.E. Short-Chain Fatty Acids in Control of Body Weight and Insulin Sensitivity. Nat. Rev. Endocrinol. 2015, 11, 577–591. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Peng, L.; Li, Z.R.; Green, R.S.; Holzman, I.R.; Lin, J. Butyrate Enhances the Intestinal Barrier by Facilitating Tight Junction Assembly via Activation of AMP-Activated Protein Kinase in Caco-2 Cell Monolayers. J. Nutr. 2009, 139, 1619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van der Beek, C.M.; Bloemen, J.G.; van den Broek, M.A.; Lenaerts, K.; Venema, K.; Buurman, W.A.; Dejong, C.H. Hepatic Uptake of Rectally Administered Butyrate Prevents an Increase in Systemic Butyrate Concentrations in Humans. J. Nutr. 2015, 145, 2019–2024. [Google Scholar] [CrossRef] [Scilit]
- Cook, S.I.; Sellin, J.H. Review Article: Short Chain Fatty Acids in Health and Disease. Aliment. Pharmacol. Ther. 1998, 12, 499–507. [Google Scholar] [CrossRef] [Scilit]
- Schönfeld, P.; Wojtczak, L. Short- and Medium-Chain Fatty Acids in Energy Metabolism: The Cellular Perspective. J. Lipid Res. 2016, 57, 943. [Google Scholar] [CrossRef] [Scilit]
- Yen, C.L.E.; Stone, S.J.; Koliwad, S.; Harris, C.; Farese, R.V. DGAT Enzymes and Triacylglycerol Biosynthesis. J. Lipid Res. 2008, 49, 2283. [Google Scholar] [CrossRef] [Scilit]
- Vogli, S.; Naska, A.; Marinos, G.; Kasdagli, M.I.; Orfanos, P. The Effect of Vitamin E Supplementation on Serum Aminotransferases in Non-Alcoholic Fatty Liver Disease (NAFLD): A Systematic Review and Meta-Analysis. Nutrients 2023, 15, 3733. [Google Scholar] [CrossRef] [Scilit]
- Mohammadian, K.; Fakhar, F.; Keramat, S.; Stanek, A. The Role of Antioxidants in the Treatment of Metabolic Dysfunction-Associated Fatty Liver Disease: A Systematic Review. Antioxidants 2024, 13, 797. [Google Scholar] [CrossRef] [Scilit]
- Jeon, J.W.; Lee, S.H.; Kim, D.; Sung, J.H. In Vitro Hepatic Steatosis Model Based on Gut–Liver-on-a-Chip. Biotechnol. Prog. 2021, 37, e3121. [Google Scholar] [CrossRef] [Scilit]
- Fedotcheva, T.A.; Beloborodova, N.V.; Fedotcheva, N.I. Common Mitochondrial Targets of Curcumin and Cinnamic Acid, the Membrane-Active Natural Phenolic Compounds. Pharmaceutics 2024, 16, 1272. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pereira, C.V.; Machado, N.G.; Oliveira, P.J. Mechanisms of Berberine (Natural Yellow 18)–Induced Mitochondrial Dysfunction: Interaction with the Adenine Nucleotide Translocator. Toxicol. Sci. 2008, 105, 408–417. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rizzo, M.; Colletti, A.; Penson, P.E.; Katsiki, N.; Mikhailidis, D.P.; Toth, P.P.; Gouni-Berthold, I.; Mancini, J.; Marais, D.; Moriarty, P.; et al. Nutraceutical Approaches to Non-Alcoholic Fatty Liver Disease (NAFLD): A Position Paper from the International Lipid Expert Panel (ILEP). Pharmacol. Res. 2023, 189, 106679. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, X.; Yin, X.; Liu, Z.; Wang, J. Non-Alcoholic Fatty Liver Disease (NAFLD) Pathogenesis and Natural Products for Prevention and Treatment. Int. J. Mol. Sci. 2022, 23, 15489. [Google Scholar] [CrossRef] [Scilit]
- Vrentzos, E.; Pavlidis, G.; Korakas, E.; Kountouri, A.; Pliouta, L.; Dimitriadis, G.D.; Lambadiari, V. Nutraceutical Strategies for Metabolic Dysfunction-Associated Steatotic Liver Disease (MASLD): A Path to Liver Health. Nutrients 2025, 17, 1657. [Google Scholar] [CrossRef] [Scilit]
- Altomare, C.; Macrì, R.; Serra, M.; Ussia, S.; Ritorto, G.; Maiuolo, J.; Muscoli, C.; Perri, E.; Mollace, V. The Potential of Nutraceutical Supplementation in Counteracting Cancer Development and Progression: A Pathophysiological Perspective. Nutrients 2025, 17, 2354. [Google Scholar] [CrossRef] [Scilit]
- Schattenberg, J.M.; Grønbæk, H.; Kliers, I.; Ladelund, S.; Long, M.T.; Nygård, S.B.; Sanyal, A.J.; Davies, M.J. Proteomic Signatures Reflect Effects of Semaglutide Treatment for MASH. JHEP Rep. 2025, 7, 101521. [Google Scholar] [CrossRef] [Scilit]
- European Medicines Agency (EMA). EMA Recommends Revoking Conditional Marketing Authorisation for Ocaliva; European Medicines Agency (EMA): Amsterdam, The Netherlands, 2024. [Google Scholar]
- Pabst, B.; Futatsugi, K.; Li, Q.; Ahn, K. Mechanistic Characterization of Long Residence Time Inhibitors of Diacylglycerol Acyltransferase 2 (DGAT2). Biochemistry 2018, 57, 6997–7010. [Google Scholar] [CrossRef] [Scilit]
- Li, C.; Li, L.; Lian, J.; Watts, R.; Nelson, R.; Goodwin, B.; Lehner, R. Roles of Acyl-CoA: Diacylglycerol Acyltransferases 1 and 2 in Triacylglycerol Synthesis and Secretion in Primary Hepatocytes. Arterioscler. Thromb. Vasc. Biol. 2015, 35, 1080–1091. [Google Scholar] [CrossRef] [Scilit]
- McKee, T.J.; Komarova, S.V. Is It Time to Reinvent Basic Cell Culture Medium? Am. J. Physiol. Cell Physiol. 2017, 312, C624–C626. [Google Scholar] [CrossRef] [Scilit]
- Padberg, F.; Höper, T.; Henkel, S.; Driesch, D.; Luch, A.; Zellmer, S. Novel Indirect Co-Culture of Immortalised Hepatocytes with Monocyte Derived Macrophages Is Characterised by pro-Inflammatory Cytokine Networks. Toxicol. Vitr. 2021, 73, 105134. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hench, J.; Hench, I.; Pujol, C.; Ipsen, S.; Brodesser, S.; Mourier, A.; Tolnay, M.; Frank, S.; Trifunović, A. A Tissue-Specific Approach to the Analysis of Metabolic Changes in Caenorhabditis Elegans. PLoS ONE 2011, 6, e28417. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rumin, J.; Bonnefond, H.; Saint-Jean, B.; Rouxel, C.; Sciandra, A.; Bernard, O.; Cadoret, J.P.; Bougaran, G. The Use of Fluorescent Nile Red and BODIPY for Lipid Measurement in Microalgae. Biotechnol. Biofuels 2015, 8, 42. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zang, M.; Xu, S.; Maitland-Toolan, K.A.; Zuccollo, A.; Hou, X.; Jiang, B.; Wierzbicki, M.; Verbeuren, T.J.; Cohen, R.A. Polyphenols Stimulate AMP-Activated Protein Kinase, Lower Lipids, and Inhibit Accelerated Atherosclerosis in Diabetic LDL Receptor–Deficient Mice. Diabetes 2006, 55, 2180–2191. [Google Scholar] [CrossRef] [Scilit]
- Shan, M.Y.; Dai, Y.; Ren, X.D.; Zheng, J.; Zhang, K.B.; Chen, B.; Yan, J.; Xu, Z.H. Berberine Mitigates Nonalcoholic Hepatic Steatosis by Downregulating SIRT1-FoxO1-SREBP2 Pathway for Cholesterol Synthesis. J. Integr. Med. 2021, 19, 545–554. [Google Scholar] [CrossRef] [Scilit]
- Sun, Y.; Yuan, X.; Zhang, F.; Han, Y.; Chang, X.; Xu, X.; Li, Y.; Gao, X. Berberine Ameliorates Fatty Acid-Induced Oxidative Stress in Human Hepatoma Cells. Sci. Rep. 2017, 7, 11340. [Google Scholar] [CrossRef] [Scilit]
- Yuan, X.; Wang, J.; Tang, X.; Li, Y.; Xia, P.; Gao, X. Berberine Ameliorates Nonalcoholic Fatty Liver Disease by a Global Modulation of Hepatic MRNA and LncRNA Expression Profiles. J. Transl. Med. 2015, 13, 24. [Google Scholar] [CrossRef] [Scilit]
- Ding, H.; Ge, K.; Fan, C.; Liu, D.; Wu, C.; Li, R.; Yan, F.J. Chlorogenic Acid Attenuates Hepatic Steatosis by Suppressing ZFP30. J. Agric. Food Chem. 2024, 72, 245–258. [Google Scholar] [CrossRef] [Scilit]
- Meng, F.; Song, C.; Liu, J.; Chen, F.; Zhu, Y.H.; Fang, X.; Cao, Q.; Ma, D.; Wang, Y.; Zhang, C. Chlorogenic Acid Modulates Autophagy by Inhibiting the Activity of ALKBH5 Demethylase, Thereby Ameliorating Hepatic Steatosis. J. Agric. Food Chem. 2023, 71, 15073–15086. [Google Scholar] [CrossRef] [Scilit]
- Liu, Y.; Wang, D.; Zhang, D.; Lv, Y.; Wei, Y.; Wu, W.; Zhou, F.; Tang, M.; Mao, T.; Li, M.; et al. Inhibitory Effect of Blueberry Polyphenolic Compounds on Oleic Acid-Induced Hepatic Steatosis in Vitro. J. Agric. Food Chem. 2011, 59, 12254–12263. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joachimiak, R.; Kaźnica, A.; Drewa, T. Influence of Sodium Butyrate on Hepatocellular Carcinoma (HepG2) and Glioblastoma (C6) Cell Lines in Vitro. Acta Pol. Pharm. Drug Res. 2007, 64, 561–563. [Google Scholar]
- Quagliariello, V.; Masarone, M.; Armenia, E.; Giudice, A.; Barbarisi, M.; Caraglia, M.; Barbarisi, A.; Persico, M. Chitosan-Coated Liposomes Loaded with Butyric Acid Demonstrate Anticancer and Anti-Inflammatory Activity in Human Hepatoma HepG2 Cells. Oncol. Rep. 2018, 41, 1476. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dierickx, P.J. Cytotoxicity Testing of 114 Compounds by the Determination of the Protein Content in Hep G2 Cell Cultures. Toxicol. Vitr. 1989, 3, 189–193. [Google Scholar] [CrossRef] [Scilit]
- Bloemen, J.G.; Venema, K.; van de Poll, M.C.; Olde Damink, S.W.; Buurman, W.A.; Dejong, C.H. Short Chain Fatty Acids Exchange across the Gut and Liver in Humans Measured at Surgery. Clin. Nutr. 2009, 28, 657–661. [Google Scholar] [CrossRef] [Scilit]
- Peters, S.G.; Pomare, E.W.; Fisher, C.A. Portal and Peripheral Blood Short Chain Fatty Acid Concentrations after Caecal Lactulose Instillation at Surgery. Gut 1992, 33, 1249. [Google Scholar] [CrossRef] [Scilit]
- Wong, J.M.W.; De Souza, R.; Kendall, C.W.C.; Emam, A.; Jenkins, D.J.A. Colonic Health: Fermentation and Short Chain Fatty Acids. J. Clin. Gastroenterol. 2006, 40, 235–243. [Google Scholar] [CrossRef] [Scilit]
- Yoshino, J.; Conte, C.; Fontana, L.; Mittendorfer, B.; Imai, S.I.; Schechtman, K.B.; Gu, C.; Kunz, I.; Fanelli, F.R.; Patterson, B.W.; et al. Resveratrol Supplementation Does Not Improve Metabolic Function in Non-Obese Women with Normal Glucose Tolerance. Cell Metab. 2012, 16, 658. [Google Scholar] [CrossRef] [Scilit]
- Smoliga, J.M.; Blanchard, O. Enhancing the Delivery of Resveratrol in Humans: If Low Bioavailability Is the Problem, What Is the Solution? Molecules 2014, 19, 17154–17172. [Google Scholar] [CrossRef] [Scilit]
- Knox, C.; Wilson, M.; Klinger, C.M.; Franklin, M.; Oler, E.; Wilson, A.; Pon, A.; Cox, J.; Chin, N.E.L.; Strawbridge, S.A.; et al. DrugBank 6.0: The DrugBank Knowledgebase for 2024. Nucleic Acids Res. 2024, 52, D1265–D1275. [Google Scholar] [CrossRef] [Scilit]
- Han, Y.; Xiang, Y.; Shi, Y.; Tang, X.; Pan, L.; Gao, J.; Bi, R.; Lai, X. Pharmacokinetics and Pharmacological Activities of Berberine in Diabetes Mellitus Treatment. Evid.-Based Complement. Altern. Med. 2021, 2021, 9987097. [Google Scholar] [CrossRef] [Scilit]
- Guan, C.; Qiao, S.; Lv, Q.; Cao, N.; Wang, K.; Dai, Y.; Wei, Z. Orally Administered Berberine Ameliorates Bleomycin-Induced Pulmonary Fibrosis in Mice through Promoting Activation of PPAR-γ and Subsequent Expression of HGF in Colons. Toxicol. Appl. Pharmacol. 2018, 343, 1–15. [Google Scholar] [CrossRef] [Scilit]
- Ai, X.; Yu, P.; Peng, L.; Luo, L.; Liu, J.; Li, S.; Lai, X.; Luan, F.; Meng, X. Berberine: A Review of Its Pharmacokinetics Properties and Therapeutic Potentials in Diverse Vascular Diseases. Front. Pharmacol. 2021, 12, 762654. [Google Scholar] [CrossRef] [Scilit]
- Clifford, M.N.; Jaganath, I.B.; Ludwig, I.A.; Crozier, A. Chlorogenic Acids and the Acyl-Quinic Acids: Discovery, Biosynthesis, Bioavailability and Bioactivity. Nat. Prod. Rep. 2017, 34, 1391–1421. [Google Scholar] [CrossRef] [Scilit]
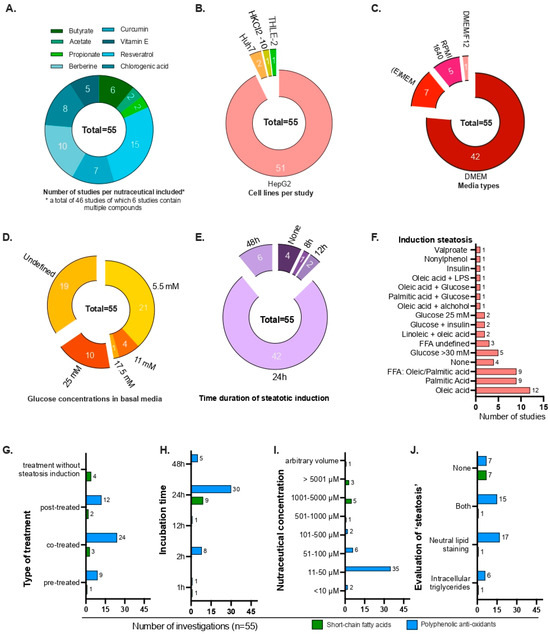
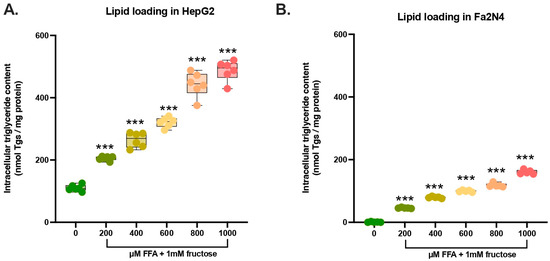
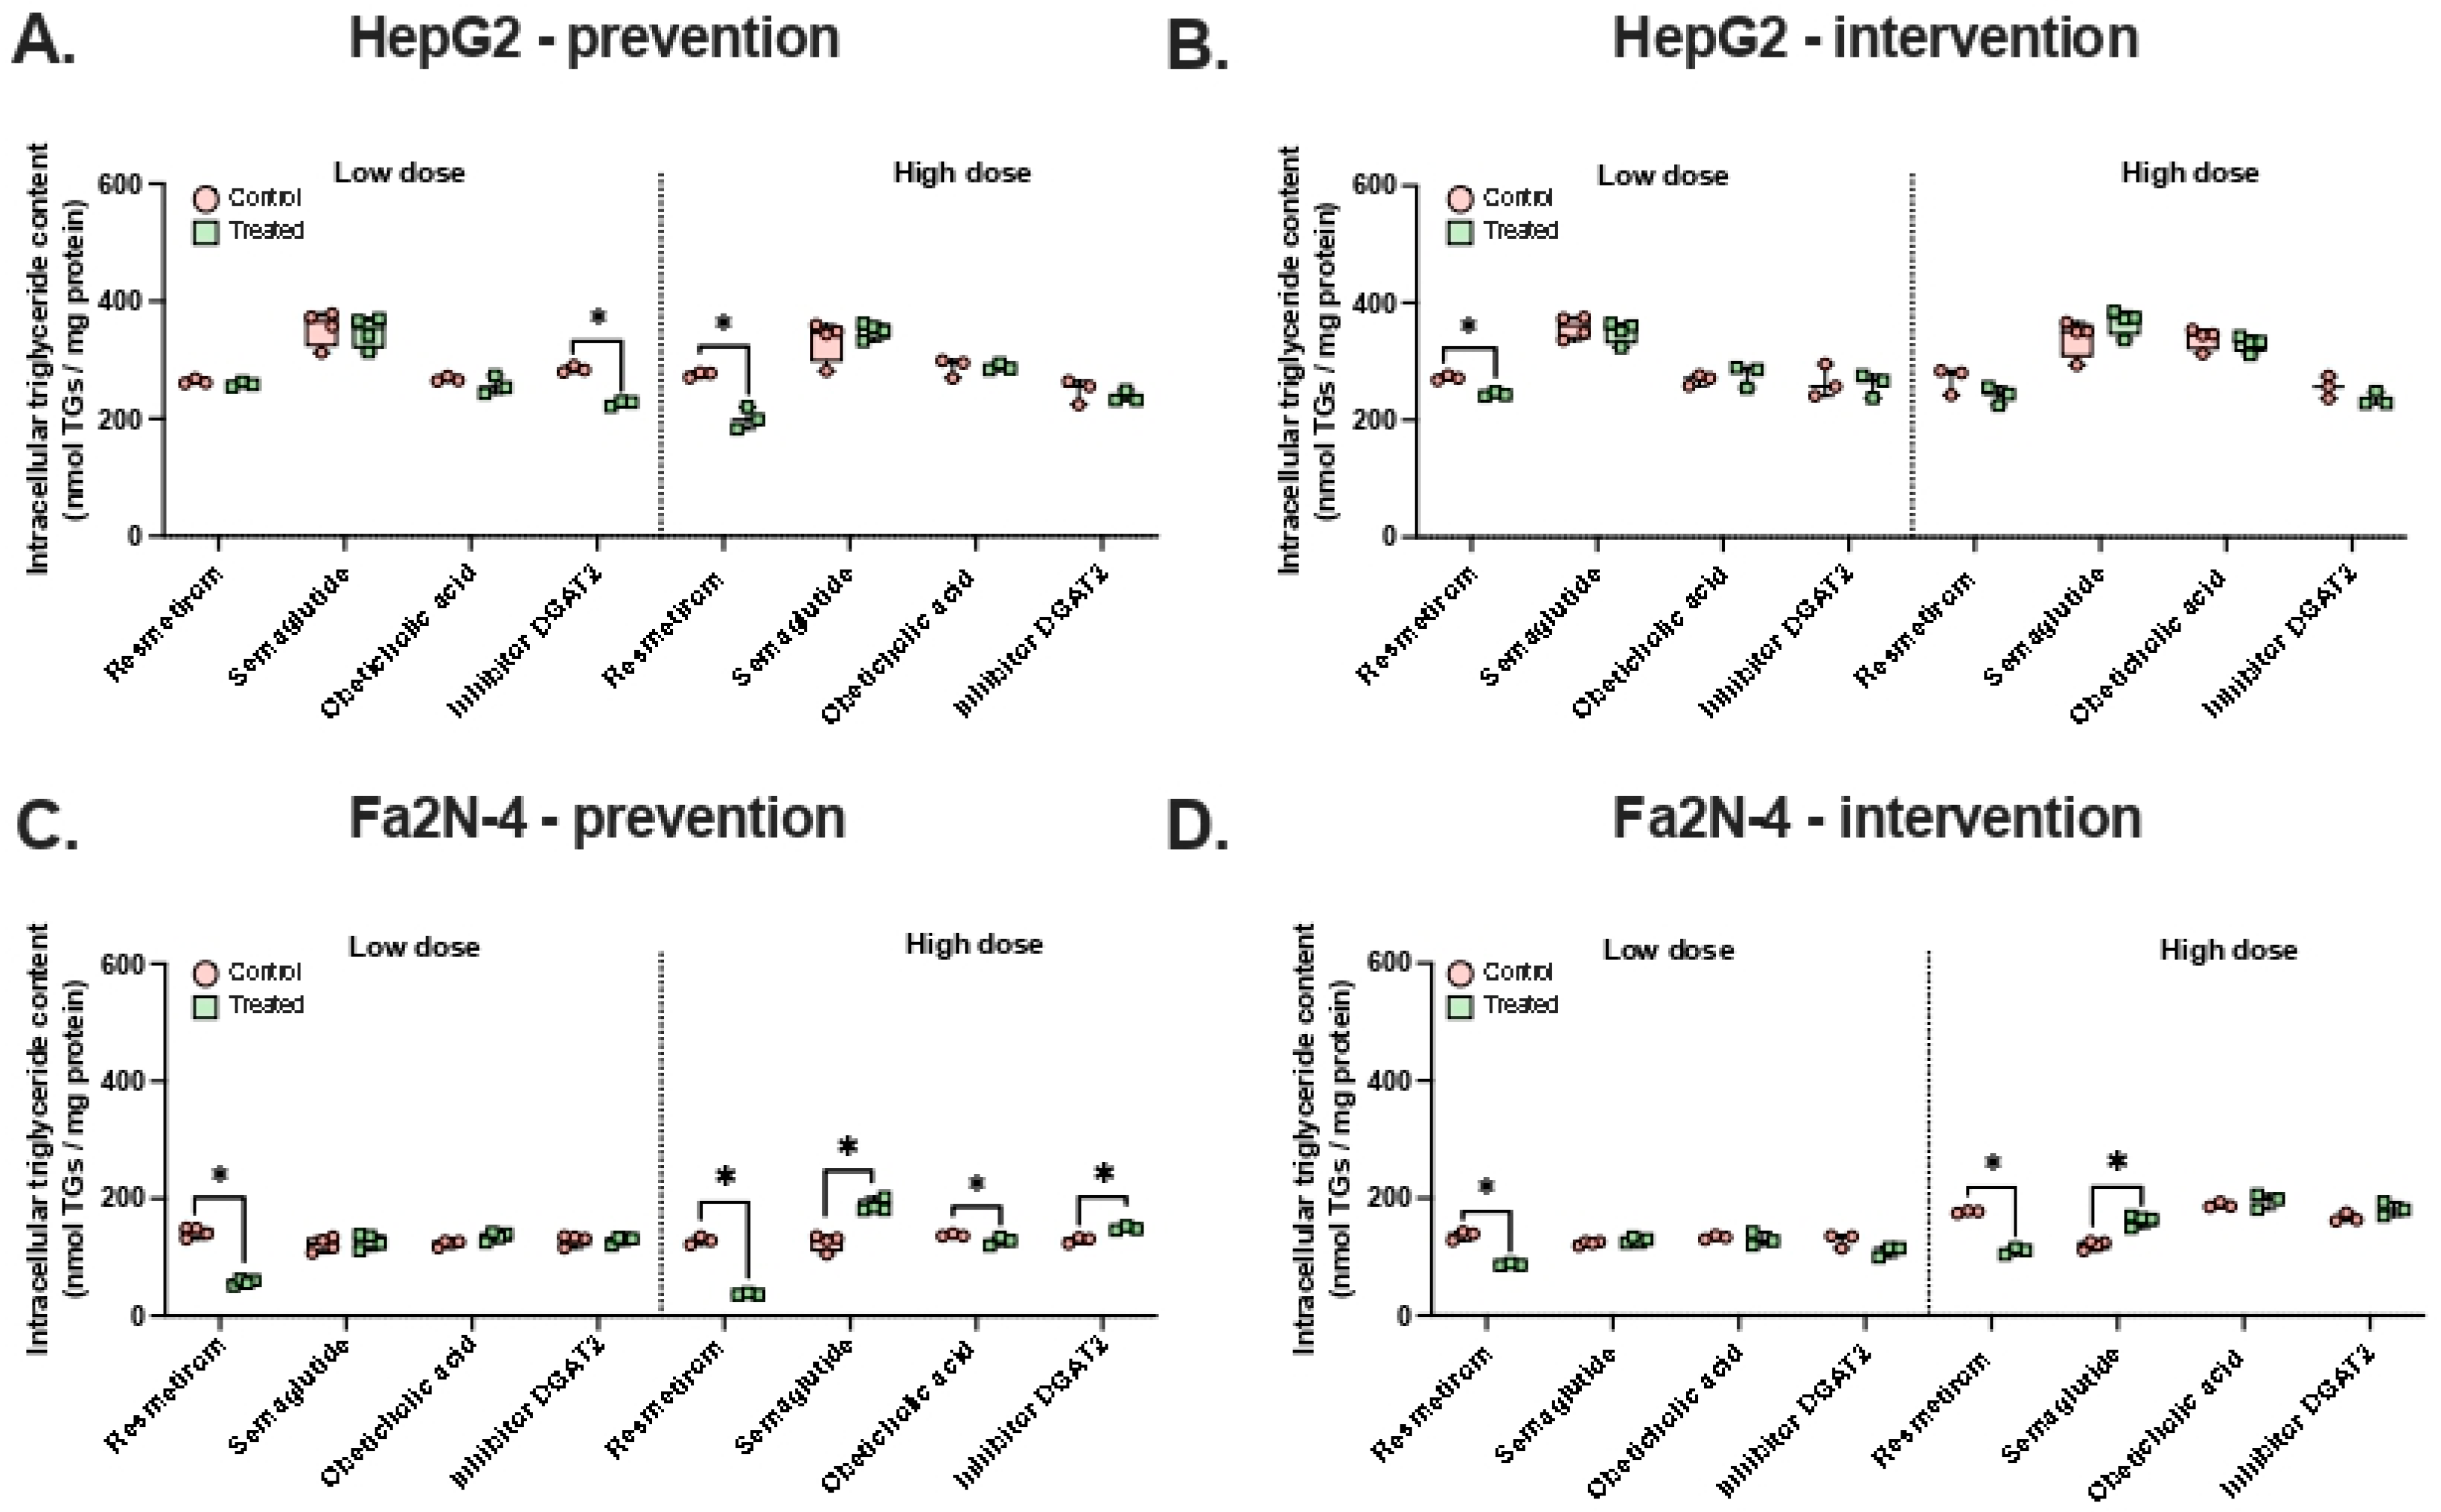
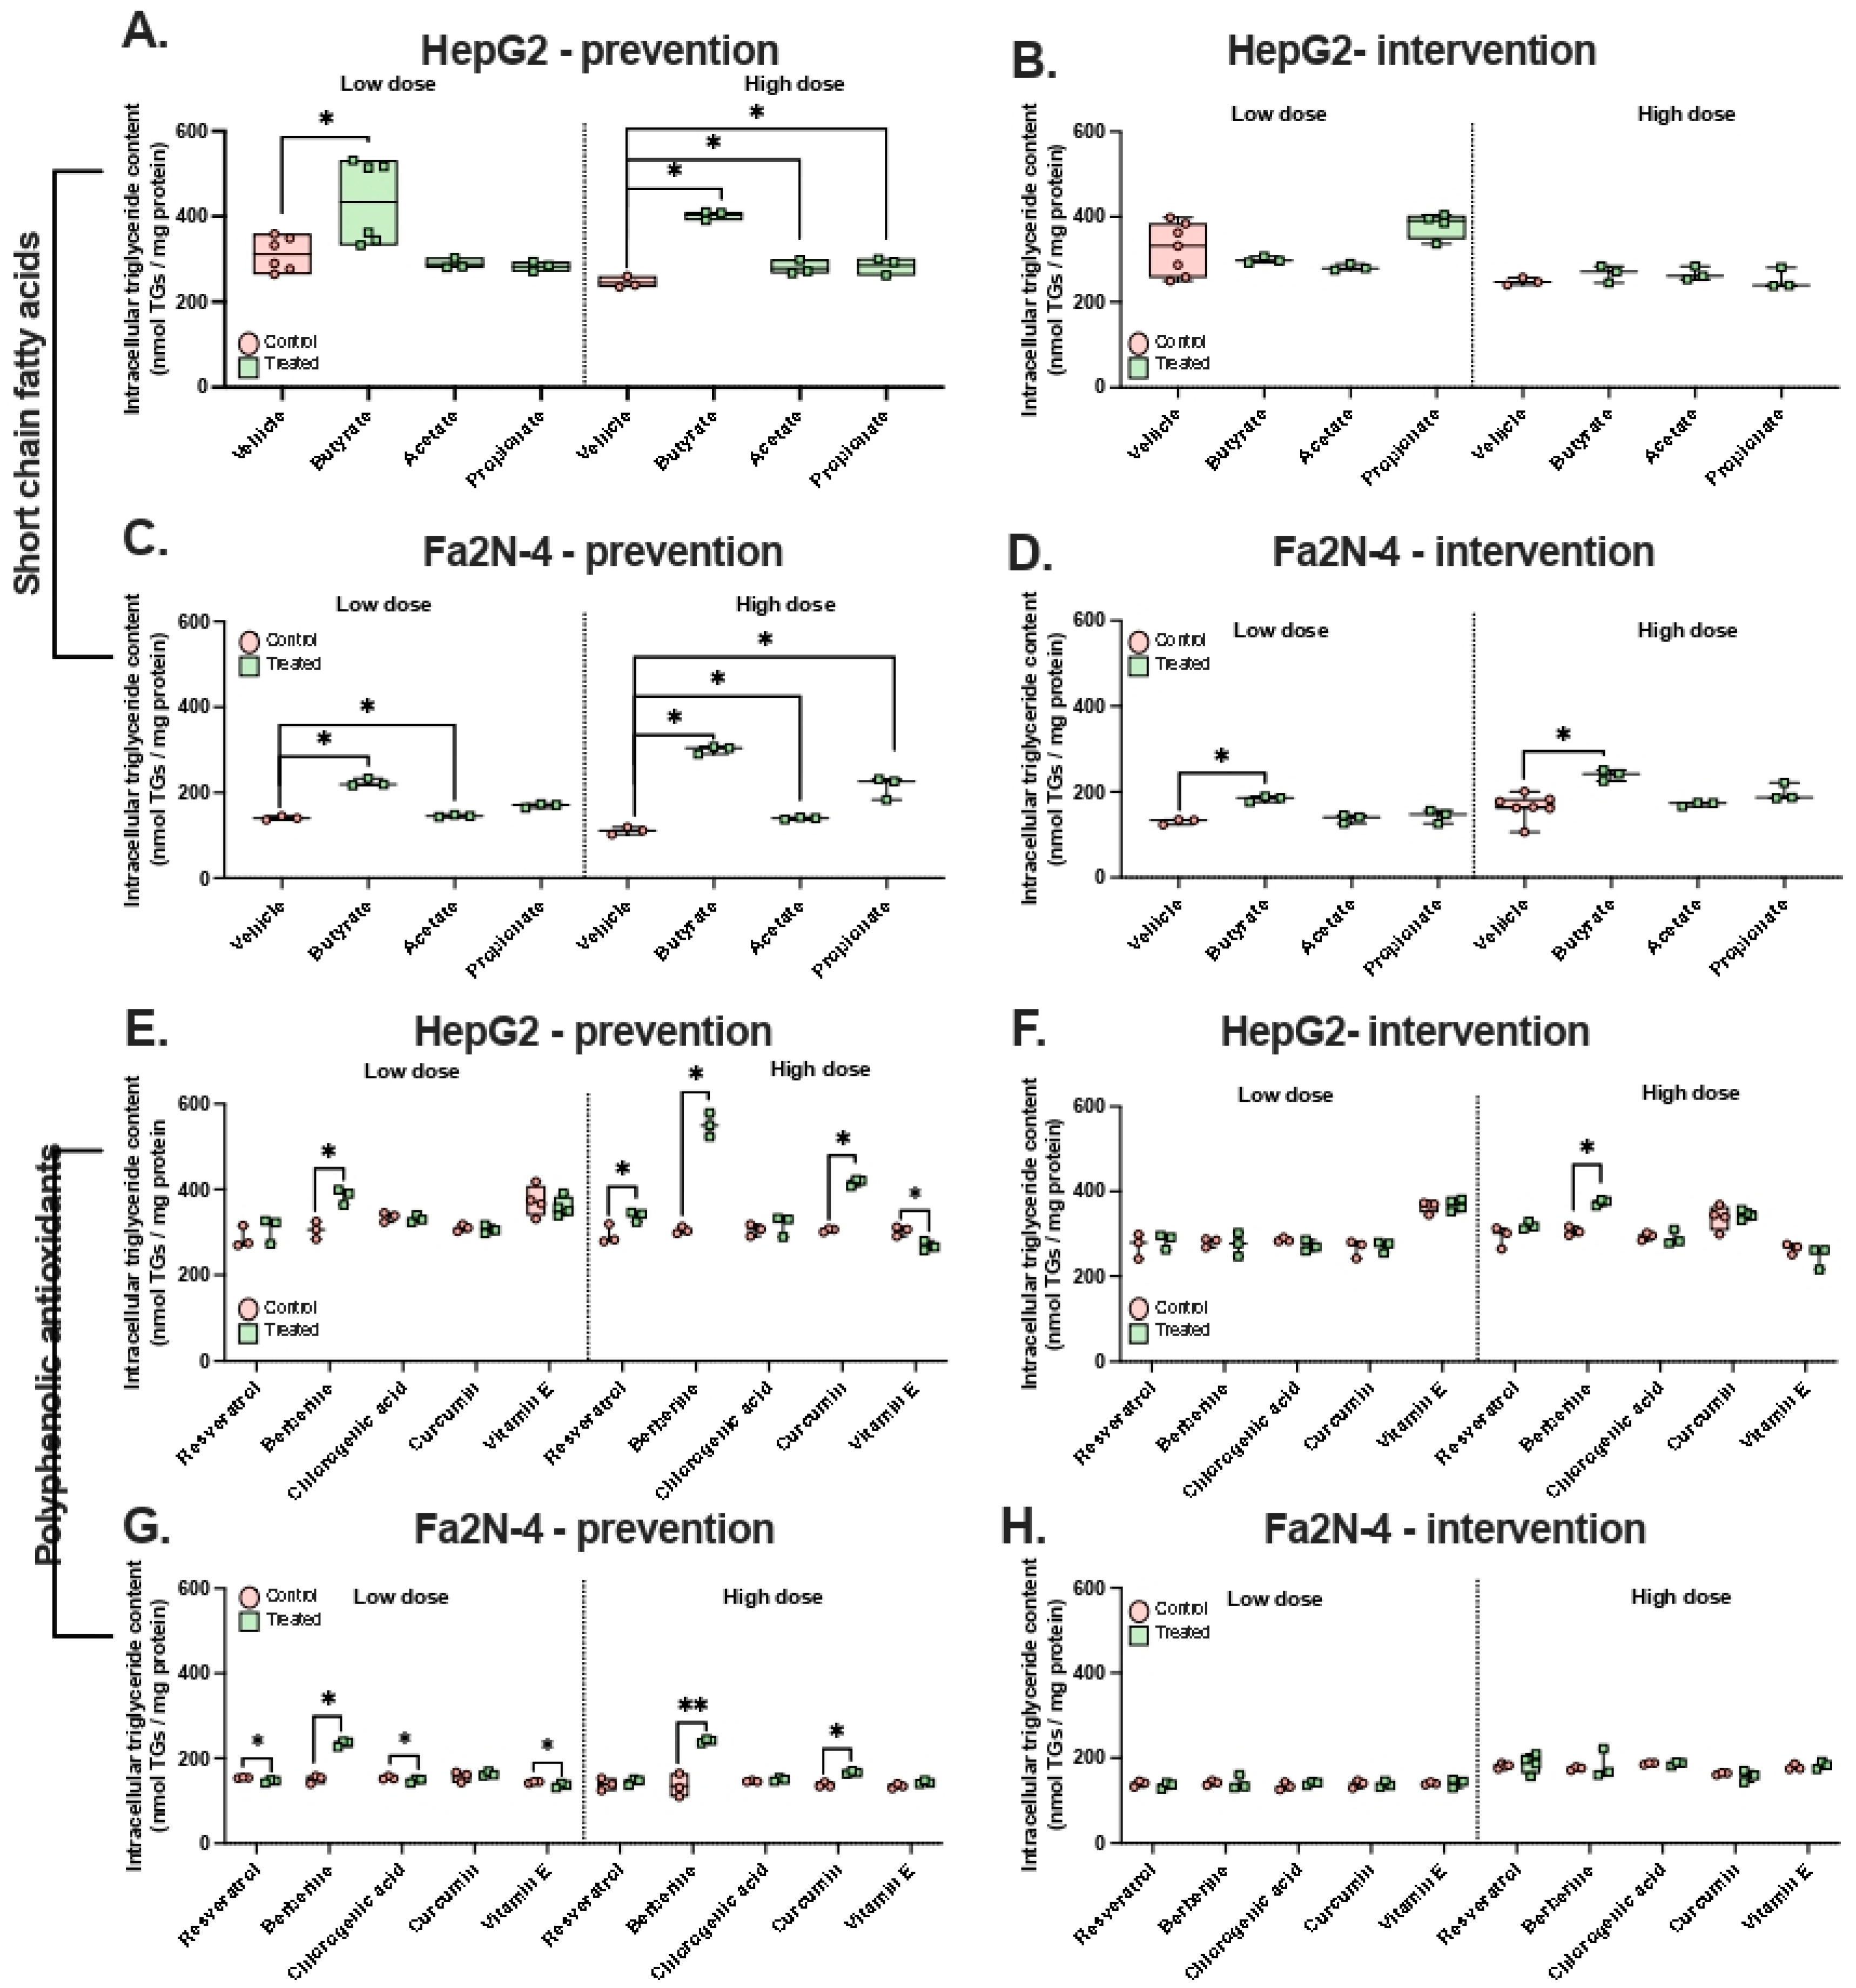

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.