


Abstract
Background: A cancer diagnosis can impact patients’ and caregivers’ lives, posing different challenging situations. In particular, breast cancer and prostate cancer are two types of cancer involving families and especially spouses in challenges linked with the diagnosis and treatment process. Caregivers are usually involved in the treatment decision-making (TDM) process concerning patients’ clinical pathway, cancer treatment, and ongoing therapies. To date, no contributions provide an exhaustive overview of the role of caregivers in cancer care and their involvement in the TDM process related to the therapies. Methods: We performed a systematic review of caregiver and patients experiences and perceptions of caregiver involvement in cancer TDM. Articles were searched on Public/Publisher MEDLINE (PubMed), Excerpta Medica Database (Embase), Medical Literature Analysis and Retrieval System Online (Medline), and American Psychological Association APA PsycINFO. Results: 17 studies were included, 10 on prostate cancer and 7 on breast cancer. According to the reviewed studies, patients and caregivers experienced the cancer diagnosis with a sense of unity. Most patients preferred to have an active or collaborative role with caregivers in TDM, feeling it was important to consult or share the decision made with their caregivers. Caregivers preferred to collaborate with patients or let patients decide by themselves after considering their opinions. Caregiver involvement could have a positive influence on the patient’s medical decisions, even if cancer diagnosis and treatments overwhelmed patients and caregivers. Conclusions: These findings highlight the importance of using a perspective that focuses on the relationship between a patient and caregivers when they receive a cancer diagnosis and have to make a treatment decision. Targeting caregiver–patient dyads, rather than individuals, is important since a supported relationship could have a protective effect on psychological distress, quality of life (QOL), and relationship satisfaction. Moreover, dyads may benefit from interventions that focus on the needs of both the patient and caregiver.
1. Introduction
A cancer diagnosis and its subsequent treatments may psychologically and practically affect patients’ and caregivers’ lives, posing different challenging situations [1]. Quite often, caregivers are the spouse/partner or the adult child of the patients; in rare cases, even friends can play this role. Patients and their family members face the dramatic experience of cancer together by going through different stages of adjustment to cancer disease [2]. In particular, breast cancer, which predominantly affects women, and prostate cancer, which affects men, are two types of cancer involving families and especially spouses in challenges linked with diagnosis and the treatment process [3,4,5]. When a patient receives the bad news of a breast or prostate cancer diagnosis, a multitude of emotional reactions, including anger, fear, and a sense of guilt, are frequent and can take the form of anxious symptoms (agitation, concentration difficulties) and/or depressive symptoms (apathy, low mood tone) [6]. Specifically, breast cancer patients may have concerns about changes in body image, sexuality, or attractiveness, difficulties, and uncertainty in planning the future, and physical toxicities that result from adjuvant therapy but also changes to the social role or adjustment in family roles [7,8]. Breast cancer is also considered a serious blow to femininity [9,10,11]. In prostate cancer patients, based on the different stages of disease progression, concerns may emerge about sexual impotence (e.g., erectile dysfunction, reduced libido) and reproductive spheres or problems related to hormonal function or incontinence [4]. These aspects can have further negative psychological implications, causing anxiety, depression, fatigue, stress, pain, and fear of cancer recurrence [12,13,14,15]. The same psychological reactions can sometimes affect patients’ partners [5,16,17,18]. Indeed, both breast- and prostate-cancer-related symptoms and side effects due to the treatment can primarily impact the intimacy of the dyads. Subsequently, they might extend their negative effects to the wider social network of the cancer patients, which includes family members, friends, and anyone who performs the role of caregiver [5,19].
Along the cancer trajectory, care options are discussed, or decisions are made. The process by which people decide is called the decision-making (DM) process. The DM process is a reasoning process based on assumptions of values, preferences, and beliefs of the decision-maker (in this case the patient), producing a final choice [20]. Specifically, breast cancer patients generally undergo surgery and/or other therapies including chemotherapy, hormone therapy, and radiation therapy. In the case of early breast cancer, decisions may concern the type of surgery (e.g., mastectomy vs. lumpectomy), reconstructive surgery, and participation in clinical trials [21]. Regarding prostate cancer, patients are faced with the difficult decision of active surveillance, radiotherapy, or surgery [22]. In both cases, the best treatment for each patient depends on both medical factors and personal assessment of the risks and benefits of each choice. Over the past decades, there has been a shift from a paternalistic approach (the patient is a passive receiver of treatment) to a patient-centered paradigm (the patient is an active participant) that allows patients to be actively involved in the treatment decision-making (TDM), and more in general, along their clinical pathway [23,24]. This way, within the concept of patient-centered care emerged the concept of a shared decision-making process (SDM) that considers patients’ individual preferences, needs, and values, which in turn, guides all clinical decisions [25,26]. However, quite often, in the oncological field, patients are accompanied by their caregivers during the visits to support the patient in the interaction and communication with the oncologists (to help understand information on the disease and its consequences, prescribed therapies and expected outcomes, side effects, and the best way to control them) and provide emotional closeness. This way, caregivers may be involved in the TDM process, stating their opinions, preferences, and beliefs on the treatment decisions [27,28,29]. Patients are defined by their relationship and depend on “significant others” to make decisions, and in this case, they may take into consideration the caregiver standpoint [12,30,31,32]. The decision-making process concerning treatment and patient care is replete with uncertainty and anxiety both for the patients and the caregivers [33]. Caregiver involvement in the oncological examinations was associated with increased patient satisfaction with care, understanding of cancer-related information, treatment adherence, and physical and mental health [34,35,36,37]. This way, caregivers may influence patient decisions regarding medical treatments, bringing with them a range of emotional reactions, interpersonal dynamics, and expectations [28,32,37,38,39,40,41]. For that reason, clinicians are moving towards family-centered models of care and the need to develop a new line of research on dyadic decision-making in the oncological domain, considering the relationship between patients and caregivers [42,43]. Until now, there was no gold standard related to caregiver involvement. However, an alignment among patient–caregiver preferences for the extent of caregiver involvement in the decision-making process may enhance the process of care for all the parties [36,44].
To date, few contributions provide an exhaustive overview of the role of caregivers in cancer care, but none of them comprehensively address newly diagnosed cancer patient and caregiver involvement in the TDM process related to therapies. Already published systematic reviews concern caregiver involvement and support in palliative care or for elder patients, who need caregiver practical assistance in care and treatment, or concern the effectiveness of psychological intervention on the triadic relationship between patients, caregivers, and physicians aimed at enhancing the triadic communication [38,45,46,47,48,49,50]. In this literature review, we focused on newly diagnosed breast and prostate cancer for a pragmatic reason, being the two most common diseases in women and men, respectively, and on the TDM process by considering the fact that some decisions related to cancer therapies can also involve the sphere of intimacy and fertility and may have a direct impact on family caregivers, who play a fundamental role in the decision, insofar as the decision has an impact on them as well. Nevertheless, we did not select only contributions where partners as caregivers were involved since we wished to explore/assess whether there are also differences in dyadic dynamics and level of compliance/agreement due to the type of relationship. Our contributions can help to identify future directions for research concerning caregiver involvement in cancer care and hints for psychological interventions to improve patient–caregiver dyadic interactions.
2. Methods
2.1. Search Strategy
The electronic search was performed through three major databases, including Public/Publisher MEDLINE (PubMed), Excerpta Medica Database (Embase), and American Psychological Association APA PsycINFO, between August to November 2020, and again in November 2022 to update the research, with no time limits. We followed PRISM guidelines to conduct our SR [51]. Original articles were considered in the English, Italian, or Spanish languages, with participants aged 18 years and up. The keywords searched in titles and abstracts included decision-making process, cancer treatment, prostate, and breast cancer, combined with terms such as caregiver involvement and patient–caregiver interaction. References in relevant systematic reviews were manually searched for additional contributions that met our inclusion criteria, although these systematic reviews were not focused on our same topic. Moreover, the reference lists of the records included were screened to identify additional relevant papers. The search was limited only to full-text articles. Due to the varied nature of keywords in this field, we developed a comprehensive list of search terms (see Figure 1 or Table A1). The present study was registered in the “Research Registry” in 2022 (ID: reviewregistry1498) and was conducted according to PRISMA guidelines.
Figure 1.
Database search terms.
2.2. Inclusion and Exclusion Criteria
Literature reviews, commentaries, editorials, book chapters, guidelines, and conference proceedings were not included in this review. An eligibility checklist summarizing the inclusion and exclusion criteria for article selection was developed (see Table 1). The studies included in this review met the following main criteria: (a) articles dealing with breast or prostate cancer patients and their caregivers, such as parents, spouses, sons, other loved ones, or close friends; (b) articles including any kind of psychological intervention promoting caregiver involvement in the breast and prostate cancer patient’s decision-making related to cancer treatment, as well as studies that did not include any psychological intervention (studies exploring/assessing the caregiver’s role in the breast and prostate cancer patient’s treatment decision-making). Regarding the research methods, we included quantitative, qualitative, and mixed methods empirical documents, assessing patient–caregiver decision-making related to cancer treatments. Specifically, qualitative research methods explain phenomena through in-depth interviews, semi-structured interviews, interviews, and focus groups; while quantitative research methods measure them through experiments, questionnaires, and surveys. The mixed methods research included both interviews or focus groups and surveys or questionnaires.
Table 1.
Eligibility Criteria (with exclusion criteria).
2.3. Screening Procedure
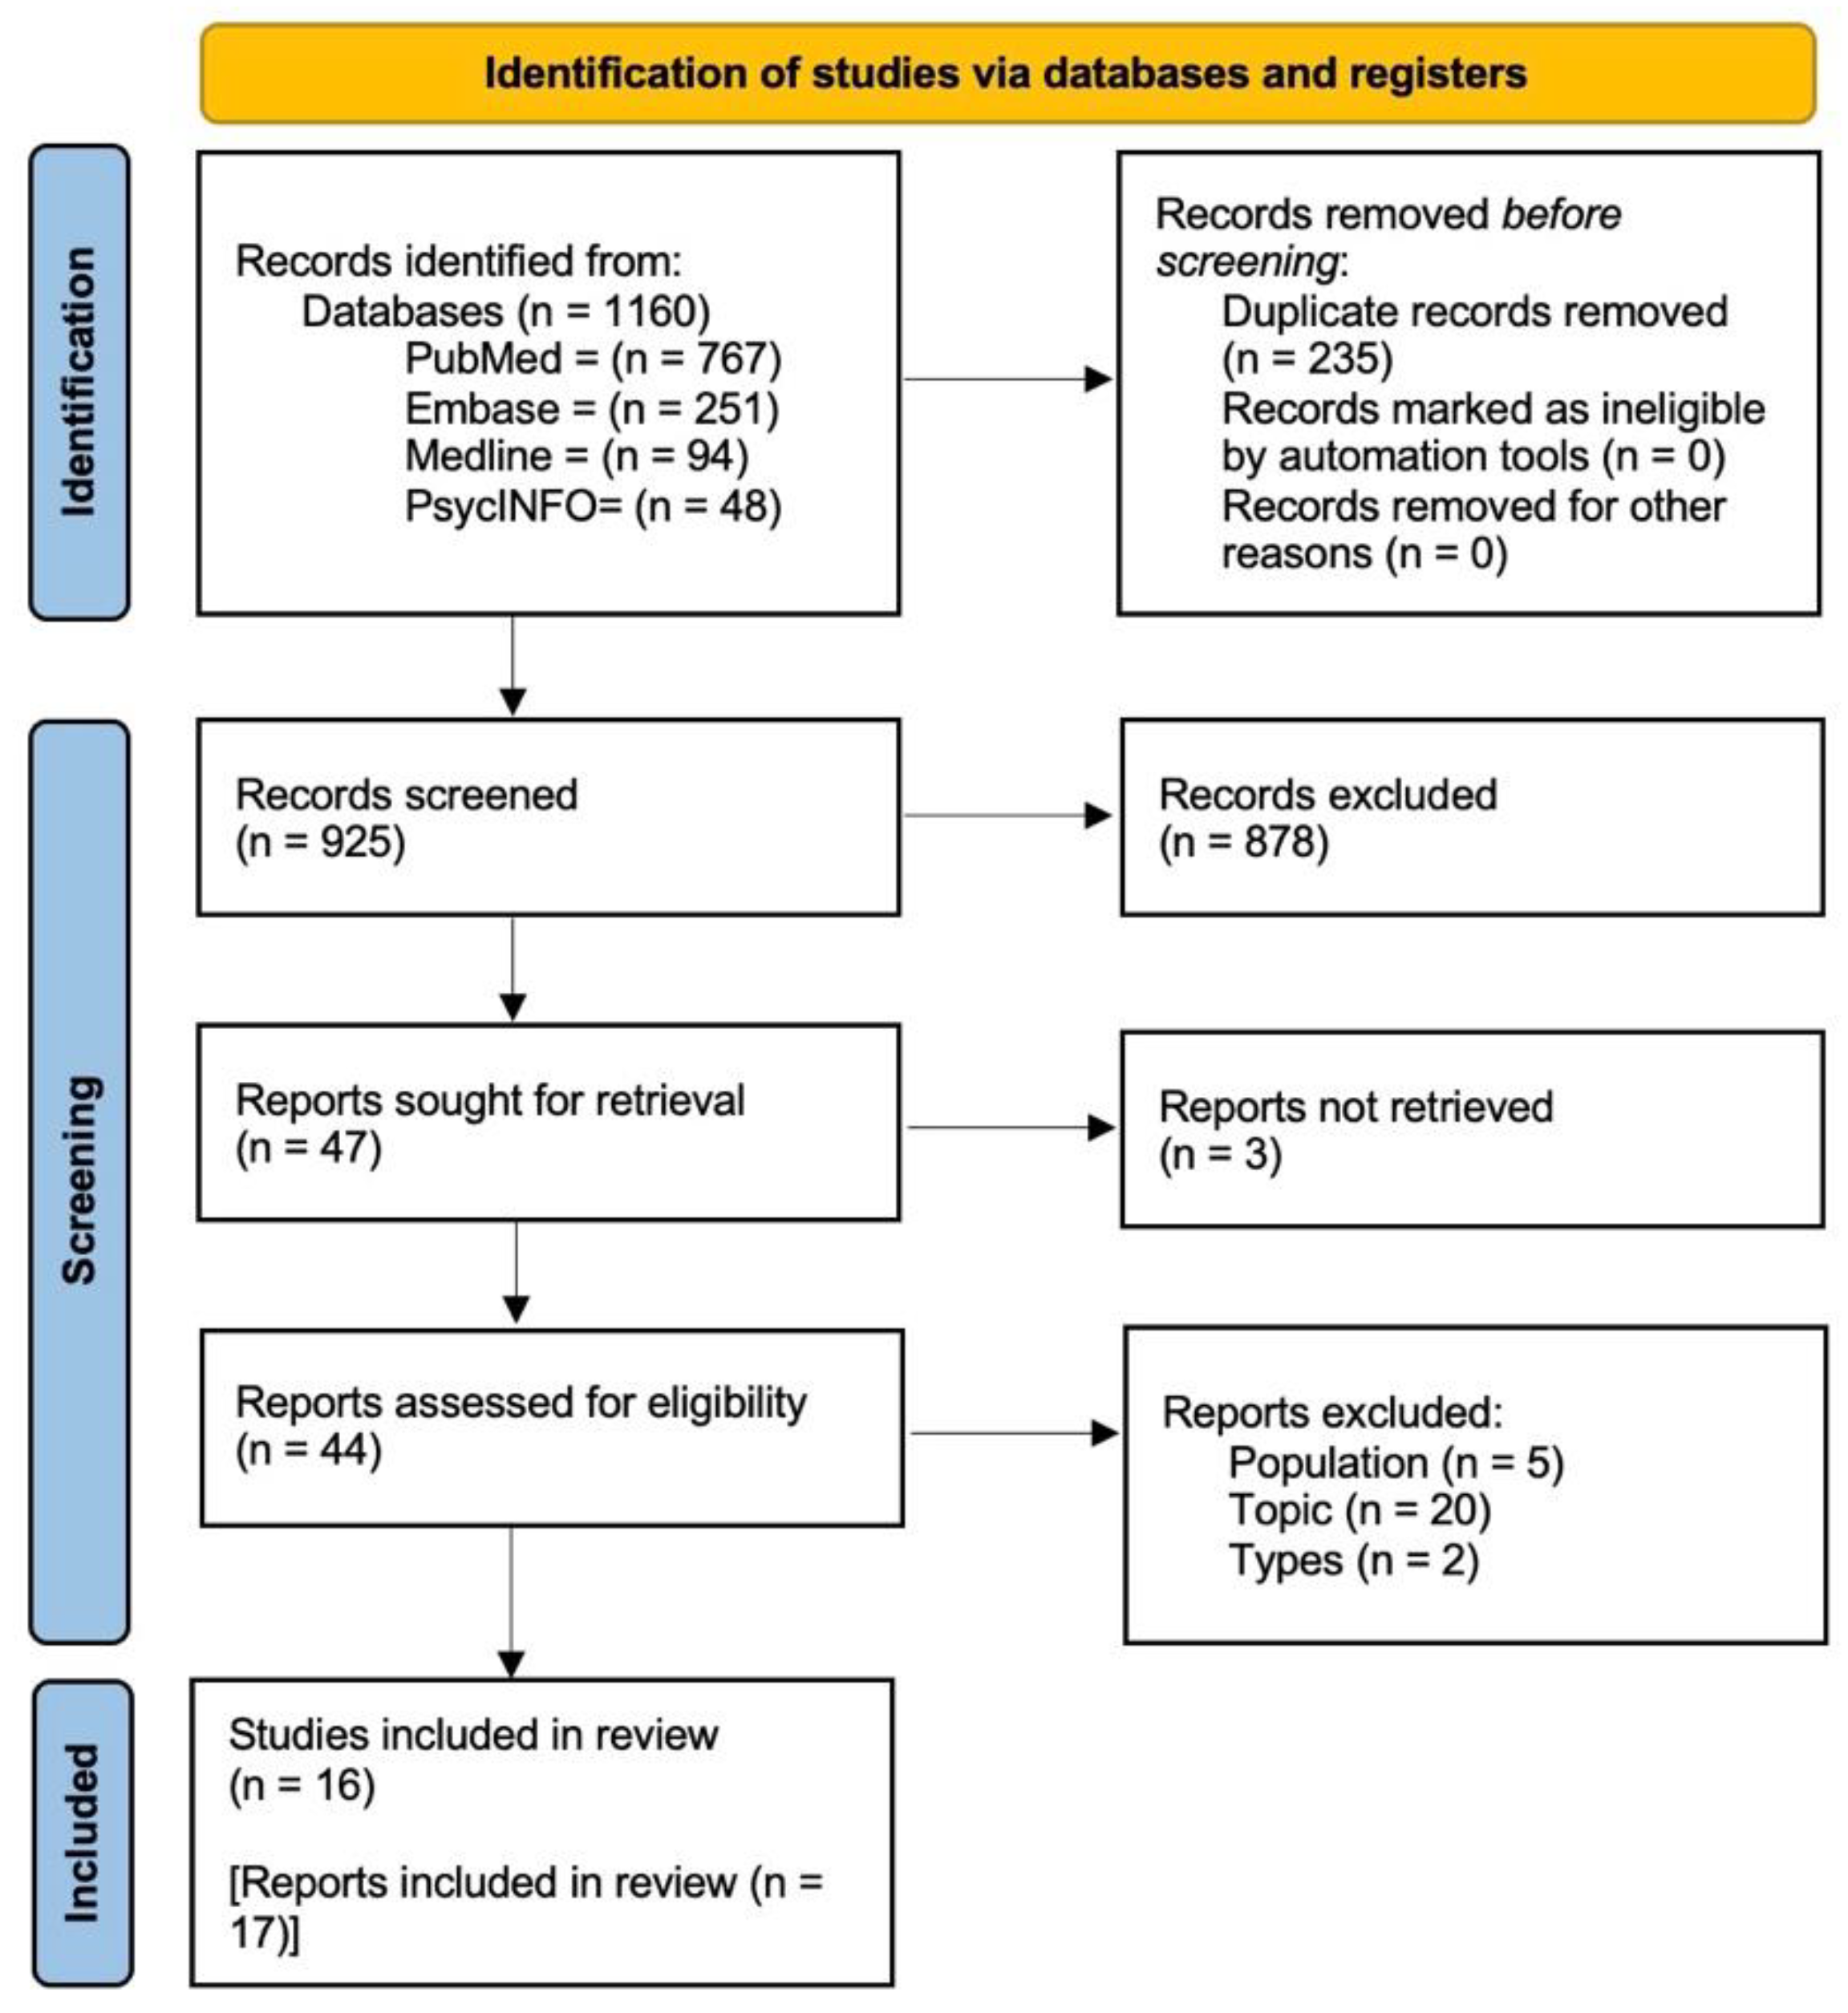
Initially, the search strategy yielded 1160 records that were screened for irrelevant or duplicate records by the first author (CC). Prior to the selection process, all records were exported in EndNote X9 reference manager. The remaining records were assessed and selected by first screening the title and the abstract, followed by a full-text reading and selection according to the predefined inclusion and exclusion criteria. The entire selection process was performed by the first author (CC) and two co-authors (SFMP and GO) independently. In case of disagreement, the three authors tried to reach a consensus. Where needed, the fourth author (SO) was involved until a consensus was reached. If the full text of an article was not available, we emailed the first or corresponding author of that article to request a PDF copy. We also used the snowball technique and citation tracking to identify additional potentially relevant publications. We selected 17 reports focused on caregiver and patient experiences and perceptions of caregiver involvement in cancer TDM. Specifically, we included 16 studies, as two reports referred to the same study. The PRISMA flowchart of the selection procedures of the studies is reported in Figure 2 [51].
Figure 2.
Preferred reporting items for systematic review and meta-analysis (PRISMA) statement flow diagram. [51].
2.4. Data Extraction
Data were extracted from each of the included reports using a custom template: country of origin, study design, data collection technique, samples/population, measurement time-point, and significant findings. Initially, the first author (CC) and the second author (SFMP) independently read and reread all the included reports, underling the relevant parts for the purpose of the review. Subsequently, the two authors discussed together the relevant parts underlined to reach a consensus on what to extract from the reports. Then, data were extracted by the first author (CC) and cross-checked for accuracy by the second author (SFMP). Reports that were hard to decide were discussed between the researchers.
We identified 11 contributions using a qualitative method, 5 contributions using the quantitative method, and 1 contribution using the mixed method. Analyzing the significant findings from each report, we found another important aspect related to shared decision-making, so we identified two macro themes: patient and caregiver involvement in cancer decision-making, and the psychological impact and its reciprocal influence on cancer in patients and caregivers.
2.5. Risk of Bias Assessment
The quality of the eligible reports was assessed using the Downs and Black’s methodological quality scale [52], a 27-item scale that provide a score on the following methodological quality scale: the reporting bias, the external validity, the internal validity, the selection bias, and the power. An overall rating of “good”, “fair”, or “poor” was given for each report. All the studies were independently rated by CC and SFMP, and any disagreements were resolved through discussion with SO. Consistently with other previous reviews, the statistical power evaluation was simplified using only two scores (1 = the sample size required to detect the significant difference was calculated; 0 = the sample size was not calculated or was insufficient to reach adequate statistical power). For qualitative studies, we considered if an analysis plan with the required sample size or quantity data for the planned analysis was included in the paper. However, the contributions included in this SR received poor scores (5–12), which means a high risk of bias due to their research methodology. Indeed, the majority of these contributions used a qualitative method and none of the rest were a randomized control trial (RCT). Considering the lack of adequate literature on the caregiver role in treatment decision making, we consider it appropriate to report in this contribution the reports that have investigated the aforementioned aspects with qualitative and/or exploratory methodology.
3. Results
A total of 17 reports met the inclusion criteria, among which 5 used a quantitative research method [41,53,54,55,56], 11 used a qualitative research method [57,58,59,60,61,62,63,64,65,66,67], and 1 used a mixed-method research method [68]. The characteristics of these reports are summarized in Table 2 for the quantitative documents, in Table 3 for the qualitative documents, and in Table 4 for the mixed methods documents.
Table 2.
Quantitative reports.
Table 3.
Qualitative reports.
Table 4.
Mixed methods report.
3.1. Characteristics of the Selected Reports
Five were carried out in the USA [41,57,62,64,67], three in Canada [53,54,60], five in Europe [58,59,61,63,65], one in Australia [66], one in Israel [55], one in China [56], and one in Oman [68].
Considering the quantitative reports, a total number of 1519 adult patient–caregiver dyads were analyzed. The majority of the dyads consisted of spouse–partner (54.51%; n = 828) or parent–son (18.24%; n = 277) with sons as caregivers, while the other dyads were composed of other family members (17.64%; n = 268, e.g., sister, cousin) or friends (8.03%; n = 122). The remaining 1.58% (n = 24) of caregivers did not provide any information about their relationship with patients. The majority of the patient sample was composed of women with breast cancer under medical treatment, such as surgery, at the initial phase of their illness (n = 1365; 89.86%). The time frame considered in the reports started from 3 to 12 months after a breast cancer diagnosis. Most women had surgery and were enrolled in the reports after breast reconstruction. Prostate cancer patients instead were enrolled at the time of diagnosis and had not yet decided on the treatment. Moreover, four reports were cross-sectional and only one study had a quasi-experimental design (pretest/post-test).
A total sample of 737 participants were interviewed in the qualitative reports, 400 (54.27%) were patients and 337 (45.73%) were caregivers. Caregivers were predominantly spouses/partners (n = 314, 93.18%), followed by other relatives (n = 16, 4.75%), among which 10 were sons; and only 3 caregivers were friends. Finally, nine caregivers (2.67%) did not specify their type of relationship with patients. Most patients had a prostate cancer diagnosis (n = 378; 94.5%). The methods employed in such reports were focus groups (1 study) and interviews (10 studies, 6 interviewing patients and caregivers separately, 5 interviewing the dyads together, and 1 mixed, interviewing them separately and together). One report used both methodologies (focus group and interview). Two of the thirteen reports had a longitudinal design, while the others were cross-sectional, except for one that was a pilot study.
One last report included in our review had a mixed methodology and enrolled 79 dyads in a time range of 24 months after the beginning of the treatment and included mostly dyads with spouses (39.2%), parents (39.2%), siblings or offspring (34.2%), and other relatives, such as nephews and stepsons (8.9%).
3.2. Shared Decision-Making between Patients and Caregivers
Reviewing quantitative studies, it was found that almost all the patients preferred to have an active or collaborative role with caregivers in the TDM process [53,54,55]. Indeed, patients felt it was important to make the final medical decision by themselves, even if only after consulting their caregiver or sharing the decisions with them [53,54,55]. Moreover, the majority of the patients reported that it was important for them to agree with their caregivers about the decision they made [55]. Finally, very few patients preferred to have a passive role, allowing their caregivers to decide [53,54,55]. Regarding the caregiver role in TDM, almost all the caregivers preferred to have a collaborative or passive role in the decision-making process [41,53,54]. However, most caregivers who took a passive role in the TDM process reported that patients decided after considering their opinion seriously [53]. Very few caregivers wanted to be active in deciding for the patients [54]. Another important aspect related to shared decision-making was the agreement between patients and caregivers. Only one study explored this topic and reported that patients and caregivers had similar ideas regarding both their attitudes toward their involvement in shared decision-making and their medical decisions [55]. Caregiver involvement in medical shared decision-making might have a positive influence on patients’ medical decisions, since greater caregiver involvement was associated with lower patient decision regret, even if the data were not statistically significant [56], and with an improvement of subjective decision quality and deliberation [41].
Regarding the results from qualitative studies, almost all the cancer patients stated that they preferred to discuss treatment options with their caregivers (e.g., partner, family members), giving importance to caregivers’ preferences, and that they felt supported by them in making treatment decisions [57,58,59,60,61,62,63,64,65,66,67]. Although patients involved caregivers in the decision-making process, feeling they were a unit/team [58,59,60,61,62,63,64,66,67], patients made the final treatment choice by themselves and the decision could be shared or not by caregivers [59,61,62,63,64,66]. Both patients and caregivers considered the decision-making process as personal and intimate, even if it was influenced by external factors, such as personalized care or psychological and emotional variables [59]. Moreover, it showed the importance of temporality in the decision-making process; some patients needed more time to decide than others [61,62]. Throughout the illness trajectory, caregivers provided emotional, instrumental and appraisal support, accompanying patients to medical appointments, remembering their screening appointments, helping them to manage daily life activities at home or to manage stressful events, encouraging and reassuring them [57,59,63,65,66,67]. In some cases, patients could perceive the caregivers’ support as inappropriate or they could feel a dissonance in their relationship; these enhanced concerns and caused conflicts [59,60].
Findings from the mixed methods study [68] reported that the majority of breast cancer patients discussed, finalized, and shared the medical decisions with caregivers (more than one family member among partners, siblings, or parents) when there was full agreement between patients and caregivers. Even caregivers reported to be involved in the TDM process and to have the role of supporting patients [68].
3.3. Psychological Impact of Cancer on Patient-Caregiver Dyads
Patients and caregivers consider a cancer diagnosis to be scary and severe, a true shock, trauma [60,62,64]. Frequently, patients and caregivers partially retreated from normal life at the beginning of their cancer journey full of concern regarding the future [60,64]. Then, patients and caregivers started to accept this new situation and tried to deal with it actively, searching for information as much as possible [57,58,60,62,64,65,66]. During the cancer trajectory, patients and caregivers lived with the illness experience as a shared challenge with a sense of being together and feeling it was important to discuss what scared them [59,60,63,64]. Patients identified a person in their family as a caregiver and received from them both emotional and instrumental support, attending and remembering medical appointments, giving reassurance, and/or hiding concern [57,63,64,65,66]. Moreover, caregivers needed to tend to their own emotional needs regarding the diagnosis to be strong for patients, and sometimes they found help in other family members or friends [57,64,65]. Indeed, patients and caregivers felt overwhelmed by the cancer diagnosis, the medical decision-making, treatments, and about their role [57,63,64]. However, when a treatment decision was made, some patients and caregivers tried to carry on as normal, while others continued to worry some of the time [60]. During the cancer trajectory, patients faced a lot of difficulties related not only to the diagnosis but also to the treatment and side-effects of treatments that were reported [61,63,65]. One of the most common concerns was related to sexuality or sexual intimacy, as well as who to tell about the cancer [60,61,63]. Due to the surgery and treatment, breast cancer patients had to face a change in their body, resulting in a loss of confidence in their nakedness [59,63]. However, male caregivers asserted that they did find their wives as attractive as before the cancer diagnosis [63]. Sometimes, patients and caregivers could disagree about whom to tell about the cancer or about seeking a second opinion or because patients perceived the support provided by caregivers as inappropriate, causing tension or conflict [59,60,66]. After the cancer diagnosis, patients underwent a great number of medical assessments to decide the best treatment, and during this period, the patient–caregiver dyad had to cope with the waiting time, and this was very anxiety-inducing, as much as when waiting for surgery [60,64]. Most of the patients and caregivers expressed a need for meeting other patients and caregivers in a similar situation to obtain psychosocial support during and after treatment [65]. Finally, the level of state-anxiety and depression that patients and caregivers experienced along the cancer trajectory decreased both in patients and caregivers over time. However, female caregiver state-anxiety levels were slightly higher than patient levels in both measurements. Finally, psychological distress did not affect the role that patients and caregivers wanted to play in medical decision-making vs. the role they actually assumed [53].
4. Discussion
Cancer can be considered a family disease [2], having an impact on both patients and caregivers, who face different challenging situations due to the cancer diagnosis [1,3,4,5]. Moreover, patients usually involve caregivers during the cancer consultation to be supported in the decision-making process, in the interaction and communication with the oncologists, and along the cancer trajectory [24,28,31,38]. With this contribution, we aimed to investigate breast and prostate cancer patient and caregiver involvement in the TDM processes related to the cancer care pathway, as well as their level of compliance. To date, no contributions provide an exhaustive overview of the role of caregivers in cancer care and their involvement in the decision-making process related to therapies.
Reviewing the studies on caregiver involvement in breast and prostate cancer patient decision-making, two macro themes emerged: the importance of patient and caregiver involvement in cancer decision-making and the psychological impact and reciprocal influence of cancer on patients and caregivers. Our review shows that most patients preferred to have an active or collaborative role with caregivers in TDM, and in both cases, patients felt the need to consult or share the decision made with their caregivers, even when caregivers did not agree with them [41,53,54,55,57,59,60,61,62,63,64,65,66,67,68]. Regarding the role of caregivers, they preferred to collaborate with patients or allow patients to decide by themselves after considering their opinions [41,53,54,55]. Only one study explored the agreement between patients and caregivers on their role in shared decision-making, reporting that patients and caregivers had similar views on both their attitudes towards their involvement in shared decision-making and their medical decisions [55]. The involvement of caregivers in shared medical decision-making could have a positive influence on patient medical decisions, reducing patient decision regret and better care for the patient [41,56].
From our results, it emerged that patients and caregivers experienced the cancer diagnosis as a shared shocking experience, with a sense of unity, that also negatively impacted both patients and caregivers on the psychological side [58,59,60,61,62,63,64,66,67]. During the cancer trajectory, patient–caregiver dyads experienced different phases: soon after the diagnosis they frequently retreated from normal life; then, they started to accept this new situation, tried to deal with it, and carried on as normal [57,58,60,62,64,65,66]. Although family caregivers provided both emotional and instrumental support, they also had to cope with their emotional needs regarding the diagnosis to be strong for the patients [57,59,63,64,65,66,67]. As a result, patients sometimes reported better scores in terms of psychological distress (e.g., anxiety and depression) than their caregiver [53]. Furthermore, there was an interdependence between the psychological aspects of patients and caregivers that did not influence the role that patients and caregivers wanted to play in the shared medical decision-making process [53]. Specifically, the cancer diagnosis and treatments overwhelmed patients and caregivers [5,16,17,18,57,63,64]. In particular, breast and prostate cancer patients were worried about sexuality and their intimacy, as already reported in the literature [4,5,7,8,9,19,60,61,63].
Finally, our results showed that along the cancer trajectory, patients and caregivers could disagree about whom to tell about cancer or about seeking a second opinion or because patients perceived the support provided by caregivers was inappropriate, causing tension or conflict [59,60,66].
4.1. Limitations
Before concluding, it is important to point out some limitations of the reviewed studies. Of the 22 included in this review, 11 were conducted in North America, 7 in Europe, 3 in Asia [55,56,68], and only 1 in Oceania [66]. Since most of the studies (18/2) included in this review were conducted in North America and Europe, the result may be limited in generalizability. Of the 5 longitudinal studies, with observation times ranging from 4 months to 18 months from baseline, none of the studies explored the entire trajectory of a family member’s caregiving experience as a dyad from cancer diagnosis to end of treatment (survivorship). Moreover, cross-sectional studies had different time points. Furthermore, it is difficult to draw final conclusions on the dyads’ psychological trends during the cancer-care pathway since the included studies used different time points of evaluation. Another limitation is that there was no balance between studies on prostate cancer and studies on breast cancer, so it was difficult to give a final conclusion. Finally, studies comparing the different roles and interdependence of the dyads among different cancers (lung, blood, and so on) might help in tailoring interventions according to the needs linked to the specific cancer diagnosis.
4.2. Recommendations for Future Research
The findings of the review indicate that caregiver involvement in cancer patients’ shared decision-making is very important because caregivers provide emotional and instrumental support to patients [57,63,64,65,66]. Moreover, patients and caregivers walk the path of treatment together and both feel negative psychological aspects that are interdependent [53,60,62,63,64]. Furthermore, cancer patients prefer to make medical decisions after consulting or sharing the decision made with their caregivers [41,53,54,55]. Considering this evidence, more research is needed to examine the interdependence among cancer dyads regarding psychological aspects, their role in the decision-making, and how they change over time according to different phases of care to facilitate the advancement of such a framework. Furthermore, given the recent COVID-19 pandemic and its countless restrictions, it could be interesting to evaluate the impact that the limitations imposed on joint visits had on the shared decision-making and on patients’ psychological well-being [69,70].
5. Conclusions
These findings highlight the importance of using a perspective that focuses on the relationship between a patient and caregivers when they receive a cancer diagnosis and must make a treatment decision. Targeting caregiver–patient dyads, rather than individuals, is important since a supported relationship could have a protective effect related to psychological distress, QOL, and relationship satisfaction. Moreover, dyads may benefit from interventions that focus on the needs of both the patient and caregiver.
Author Contributions
Conceptualization, C.C. and S.O.; methodology, C.C., S.F.M.P. and G.O.; writing—original draft preparation, C.C., S.F.M.P., G.O. and S.O.; writing—review and editing, C.C., S.F.M.P. and S.O.; supervision, G.P. All authors have read and agreed to the published version of the manuscript.
Funding
The present work was partially supported by the Italian Ministry of Health with Ricerca Corrente and 5 ȕ 1000 funds for IEO European Institute of Oncology IRCSS.
Institutional Review Board Statement
The study was conducted according to the guidelines of the Declaration of Helsinki, and approved by the Ethical Committee of the European Institute of Oncology (protocol code R1598/21-IEO 1702, approval date 15 December 2021).
Informed Consent Statement
Not applicable.
Data Availability Statement
The data presented in this study are available on request from the corresponding author.
Acknowledgments
Clizia Cincidda is supported by the European School of Molecular Medicine (SEMM).
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Table A1.
Search Strategy.
References
- Woźniak, K.; Iżycki, D. Cancer: A family at risk. Menopausal Rev. 2014, 4, 253–261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Minuchin, S. Families and Family Therapy; Harvard University: Cambridge, MA, USA, 1974. [Google Scholar]
- Kim, Y.; Given, B.A. Quality of life of family caregivers of cancer survivors. Cancer 2008, 112, 2556–2568. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Northouse, L.L.; Mood, D.W.; Schafenacker, A.; Montie, J.E.; Sandler, H.M.; Forman, J.D.; Hussain, M.; Pienta, K.J.; Smith, D.C.; Kershaw, T. Randomized clinical trial of a family intervention for prostate cancer patients and their spouses. Cancer 2007, 110, 2809–2818. [Google Scholar] [CrossRef] [Scilit]
- Segrin, C.; Badger, T.A. Psychological distress in different social network members of breast and prostate cancer survivors. Res. Nurs. Health 2010, 33, 450–464. [Google Scholar] [CrossRef] [Scilit]
- Saita, E.; Acquati, C.; Molgora, S. Promoting Patient and Caregiver Engagement to Care in Cancer. Front. Psychol. 2016, 7, 1660. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dorros, S.M.; Card, N.A.; Segrin, C.; Badger, T.A. Interdependence in women with breast cancer and their partners: An interindividual model of distress. J. Consult. Clin. Psychol. 2010, 78, 121–125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manne, S.; Sherman, M.; Ross, S.; Ostroff, J.; Heyman, R.E.; Fox, K. Couples’ Support-Related Communication, Psychological Distress, and Relationship Satisfaction Among Women With Early Stage Breast Cancer. J. Consult. Clin. Psychol. 2004, 72, 660–670. [Google Scholar] [CrossRef] [Scilit]
- Ganz, P.A. Psychological and social aspects of breast cancer. Oncology 2008, 22, 642–646, 650; discussion 650, 653. [Google Scholar]
- Oliveri, S.; Marton, G.; Vergani, L.; Cutica, I.; Gorini, A.; Spinella, F.; Pravettoni, G. Genetic Testing Consumers in Italy: A Preliminary Investigation of the Socio-Demographic Profile, Health-Related Habits, and Decision Purposes. Front. Public Health 2020, 8, 511. [Google Scholar] [CrossRef] [Scilit]
- Oliveri, S.; Durosini, I.; Cutica, I.; Cincidda, C.; Spinella, F.; Baldi, M.; Gorini, A.; Pravettoni, G. Health orientation and individual tendencies of a sample of Italian genetic testing consumers. Mol. Genet. Genom. Med. 2020, 8, e1291. [Google Scholar] [CrossRef] [Scilit]
- Cincidda, C.; Oliveri, S.; Sanchini, V.; Pravettoni, G. The role of caregivers in the clinical pathway of patients newly diagnosed with breast and prostate cancer: A study protocol. Front. Psychol. 2022, 13, 962634. [Google Scholar] [CrossRef] [Scilit]
- Cincidda, C.; Pizzoli, S.F.M.; Pravettoni, G. Remote Psychological Interventions for Fear of Cancer Recurrence: Scoping Review. JMIR Cancer 2022, 8, e29745. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Sousa, A.; Sonavane, S.; Mehta, J. Psychological aspects of prostate cancer: A clinical review. Prostate Cancer Prostatic Dis. 2012, 15, 120–127. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Muzzatti, B.; Bomben, F.; Flaiban, C.; Piccinin, M.; Annunziata, M.A. Quality of life and psychological distress during cancer: A prospective observational study involving young breast cancer female patients. BMC Cancer 2020, 20, 758. [Google Scholar] [CrossRef] [Scilit]
- Edwards, B.; Clarke, V. The psychological impact of a cancer diagnosis on families: The influence of family functioning and patients’ illness characteristics on depression and anxiety. Psychooncology 2004, 13, 562–576. [Google Scholar] [CrossRef] [Scilit]
- Hodges, L.J.; Humphris, G.M.; Macfarlane, G. A meta-analytic investigation of the relationship between the psychological distress of cancer patients and their carers. Soc. Sci. Med. 2005, 60, 1–12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stenberg, U.; Ruland, C.M.; Miaskowski, C. Review of the literature on the effects of caring for a patient with cancer. Psychooncology 2010, 19, 1013–1025. [Google Scholar] [CrossRef] [Scilit]
- Sandgren, A.K.; Mullens, A.B.; Erickson, S.C.; Romanek, K.M.; McCaul, K.D. Confidant and breast cancer patient reports of quality of life. Qual. Life Res. 2004, 13, 155–160. [Google Scholar] [CrossRef] [Scilit]
- Oliveri, S.; Cincidda, C.; Ongaro, G.; Cutica, I.; Gorini, A.; Spinella, F.; Fiorentino, F.; Baldi, M.; Pravettoni, G. What people really change after genetic testing (GT) performed in private labs: Results from an Italian study. Eur. J. Hum. Genet. 2022, 30, 62–72. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Waks, A.G.; Winer, E.P. Breast Cancer Treatment. JAMA 2019, 321, 288–300. [Google Scholar] [CrossRef] [Scilit]
- Scherr, K.; Delaney, R.K.; Ubel, P.; Kahn, V.C.; Hamstra, D.; Wei, J.T.; Fagerlin, A. Preparing Patients with Early Stage Prostate Cancer to Participate in Clinical Appointments Using a Shared Decision Making Training Video. Med. Decis. Mak. 2022, 42, 364–374. [Google Scholar] [CrossRef] [Scilit]
- Arnaboldi, P.; Oliveri, S.; Vergani, L.; Marton, G.; Guiddi, P.; Busacchio, D.; Didier, F.; Pravettoni, G. The clinical-care focused psychological interview (CLiC): A structured tool for the assessment of cancer patients’ needs. Ecancermedicalscience 2020, 14, 1000. [Google Scholar] [CrossRef] [Scilit]
- Pravettoni, G.; Cutica, I.; Righetti, S.; Mazzocco, K. Decisions and involvement of cancer patient survivors: A moral imperative. J. Healthc. Leadersh. 2016, 8, 121–125. [Google Scholar] [CrossRef] [Scilit]
- Marton, G.; Pizzoli, S.F.M.; Vergani, L.; Mazzocco, K.; Monzani, D.; Bailo, L.; Pancani, L.; Pravettoni, G. Patients’ health locus of control and preferences about the role that they want to play in the medical decision-making process. Psychol. Health Med. 2021, 26, 260–266. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Russo, G.A.; Oliveri, S.; Cincidda, C.; Guiddi, P.; Pravettoni, G. Exploring public attitude toward biofeedback technologies: Knowledge, preferences and personality tendencies. J. Public Health Res. 2020, 9, 440–446. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dionne-Odom, J.N.; Ejem, D.; Wells, R.; Barnato, A.E.; Taylor, R.A.; Rocque, G.B.; Turkman, Y.E.; Kenny, M.; Ivankova, N.V.; Bakitas, M.A.; et al. How family caregivers of persons with advanced cancer assist with upstream healthcare decision-making: A qualitative study. PLoS ONE 2019, 14, e0212967. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Laidsaar-Powell, R.; Butow, P.; Charles, C.; Gafni, A.; Entwistle, V.; Epstein, R.; Juraskova, I. The TRIO Framework: Conceptual insights into family caregiver involvement and influence throughout cancer treatment decision-making. Patient Educ. Couns. 2017, 100, 2035–2046. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ullrich, A.; Theochari, M.; Bergelt, C.; Marx, G.; Woellert, K.; Bokemeyer, C.; Oechsle, K. Ethical challenges in family caregivers of patients with advanced cancer–a qualitative study. BMC Palliat. Care 2020, 19, 70. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gómez-Vírseda, C.; de Maeseneer, Y.; Gastmans, C. Relational autonomy in end-of-life care ethics: A contextualized approach to real-life complexities. BMC Med. Ethics 2020, 21, 50. [Google Scholar] [CrossRef] [Scilit]
- Del Piccolo, L.; Goss, C.; Bottacini, A.; Rigoni, V.; Mazzi, M.; Deledda, G.; Ballarin, M.; Molino, A.; Fiorio, E.; Zimmermann, C. Asking questions during breast cancer consultations: Does being alone or being accompanied make a difference? Eur. J. Oncol. Nurs. 2014, 18, 299–304. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Laidsaar-Powell, R.; Butow, P.; Bu, S.; Charles, C.; Gafni, A.; Fisher, A.; Juraskova, I. Family involvement in cancer treatment decision-making: A qualitative study of patient, family, and clinician attitudes and experiences. Patient Educ. Couns. 2016, 99, 1146–1155. [Google Scholar] [CrossRef] [Scilit]
- Temel, J.S.; McCannon, J.; Greer, J.A.; Jackson, V.A.; Rn, P.O.; Pirl, W.; Lynch, T.J.; Billings, J.A. Aggressiveness of care in a prospective cohort of patients with advanced NSCLC. Cancer 2008, 113, 826–833. [Google Scholar] [CrossRef] [Scilit]
- DuBenske, L.L.; Gustafson, D.H.; Shaw, B.R.; Cleary, J.F. Web-Based Cancer Communication and Decision Making Systems: Connecting Patients, Caregivers, and Clinicians for Improved Health Outcomes. Med. Decis. Mak. 2010, 30, 732–744. [Google Scholar] [CrossRef] [Scilit]
- DuBenske, L.L.; Chih, M.-Y.; Gustafson, D.H.; Dinauer, S.; Cleary, J.F. Caregivers’ participation in the oncology clinic visit mediates the relationship between their information competence and their need fulfillment and clinic visit satisfaction. Patient Educ. Couns. 2010, 81, S94–S99. [Google Scholar] [CrossRef] [Scilit]
- Joosten, E.A.G.; DeFuentes-Merillas, L.; de Weert, G.H.; Sensky, T.; van der Staak, C.P.F.; de Jong, C.A.J. Systematic Review of the Effects of Shared Decision-Making on Patient Satisfaction, Treatment Adherence and Health Status. Psychother. Psychosom. 2008, 77, 219–226. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hobbs, G.S.; Landrum, M.B.; Arora, N.K.; Ganz, P.A.; van Ryn, M.; Weeks, J.C.; Mack, J.W.; Keating, N.L. The role of families in decisions regarding cancer treatments. Cancer 2015, 121, 1079–1087. [Google Scholar] [CrossRef] [Scilit]
- Laidsaar-Powell, R.; Butow, P.; Bu, S.; Charles, C.; Gafni, A.; Lam, W.; Jansen, J.; McCaffery, K.; Shepherd, H.; Tattersall, M.; et al. Physician–patient–companion communication and decision-making: A systematic review of triadic medical consultations. Patient Educ. Couns. 2013, 91, 3–13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Longacre, M.L.; Miller, M.F.; Golant, M.; Zaleta, A.K.; Buzaglo, J.S. Care and Treatment Decisions in Cancer: The Role of the Family Caregiver. J. Oncol. Navig. Surviv. 2018, 9, 354–362. [Google Scholar]
- Longacre, M.L.; Applebaum, A.J.; Buzaglo, J.S.; Miller, M.F.; Golant, M.; Rowland, J.H.; Given, B.; Dockham, B.; Northouse, L. Reducing informal caregiver burden in cancer: Evidence-based programs in practice. Transl. Behav. Med. 2018, 8, 145–155. [Google Scholar] [CrossRef] [Scilit]
- Veenstra, C.M.; Wallner, L.P.; Abrahamse, P.H.; Janz, N.K.; Katz, S.J.; Hawley, S.T. Understanding the engagement of key decision support persons in patient decision making around breast cancer treatment. Cancer 2019, 125, 1709–1716. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Faccio, F.; Renzi, C.; Crico, C.; Kazantzaki, E.; Kondylakis, H.; Koumakis, L.; Marias, K.; Pravettoni, G. Development of an eHealth tool for cancer patients: Monitoring psychoemotional aspects with the family resilience (FaRe) questionnaire. Ecancermedicalscience 2018, 12, 852. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Petrocchi, S.; Marzorati, C.; Masiero, M. “We-Diseases” and Dyadic Decision-Making Processes: A Critical Perspective. Public Health Genom. 2022, 25, 120–124. [Google Scholar] [CrossRef] [Scilit]
- Krieger, J.L. Family Communication About Cancer Treatment Decision Making A Description of the DECIDE Typology. Ann. Int. Commun. Assoc. 2014, 38, 279–305. [Google Scholar] [CrossRef] [Scilit]
- Dijkman, B.L.; Luttik, M.L.; van der Wal-Huisman, H.; Paans, W.; van Leeuwen, B.L. Factors influencing family involvement in treatment decision-making for older patients with cancer: A scoping review. J. Geriatr. Oncol. 2022, 13, 391–397. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kraun, L.; de Vliegher, K.; Vandamme, M.; Holtzheimer, E.; Ellen, M.; van Achterberg, T. Older peoples’ and informal caregivers’ experiences, views, and needs in transitional care decision-making: A systematic review. Int. J. Nurs. Stud. 2022, 134, 104303. [Google Scholar] [CrossRef] [Scilit]
- Hopkinson, J.B.; Brown, J.C.; Okamoto, I.; Addington-Hall, J.M. The Effectiveness of Patient-Family Carer (Couple) Intervention for the Management of Symptoms and Other Health-Related Problems in People Affected by Cancer: A Systematic Literature Search and Narrative Review. J. Pain Symptom Manag. 2012, 43, 111–142. [Google Scholar] [CrossRef] [Scilit]
- Northouse, L.L.; Katapodi, M.C.; Song, L.; Zhang, L.; Mood, D.W. Interventions with Family Caregivers of Cancer Patients: Meta-Analysis of Randomized Trials. CA Cancer J. Clin. 2010, 60, 317–339. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Symmons, S.M.; Ryan, K.; Aoun, S.M.; E Selman, L.; Davies, A.N.; Cornally, N.; Lombard, J.; McQuilllan, R.; Guerin, S.; O’Leary, N.; et al. Decision-making in palliative care: Patient and family caregiver concordance and discordance—Systematic review and narrative synthesis. BMJ Support. Palliat. Care 2022. [Google Scholar] [CrossRef] [Scilit]
- Tulsky, J.A.; Steinhauser, K.E.; LeBlanc, T.W.; Bloom, N.; Lyna, P.R.; Riley, J.; Pollak, K.I. Triadic agreement about advanced cancer treatment decisions: Perceptions among patients, families, and oncologists. Patient Educ. Couns. 2022, 105, 982–986. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. Syst. Rev. 2021, 10, 89. [Google Scholar] [CrossRef] [Scilit]
- Downs, S.H.; Black, N. The feasibility of creating a checklist for the assessment of the methodological quality both of randomised and non-randomised studies of health care interventions. J. Epidemiol. Community Health 1998, 52, 377–384. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davison, B.J.; Goldenberg, S.L.; Gleave, M.E.; Degner, L.F. Provision of individualized information to men and their partners to facilitate treatment decision making in prostate cancer. Oncol. Nurs. Forum 2003, 30, 107–114. [Google Scholar] [CrossRef] [Scilit]
- Davison, B.J.; Gleave, M.E.; Goldenberg, S.L.; Degner, L.F.; Hoffart, D.; Berkowitz, J. Assessing information and decision preferences of men with prostate cancer and their partners. Cancer Nurs. 2002, 25, 42–49. [Google Scholar] [CrossRef] [Scilit]
- Gilbar, R.; Gilbar, O. The medical decision-making process and the family: The case of breast cancer patients and their husbands. Bioethics 2009, 23, 183–192. [Google Scholar] [CrossRef] [Scilit]
- Kuo, N.T.; Kuo, Y.L.; Lai, H.W.; Ko, N.Y.; Fang, S.Y. The influence of partner involvement in the decision-making process on body image and decision regret among women receiving breast reconstruction. Support. Care Cancer 2019, 27, 1721–1728. [Google Scholar] [CrossRef] [Scilit]
- Boehmer, U.; Babayan, R.K. A pilot study to determine support during the pre-treatment phase of early prostate cancer. Psychooncology 2005, 14, 442–449. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Docherty, A.; Cannon, P.; Brothwell, P.D.; Symons, M.; Pct, B. The Impact of Inadequate Knowledge on Patient and Spouse Experience of Prostate Cancer Cancer nurse specialist Experience Knowledge Patient preference Prostate cancer. Cancer Nurs. 2007, 30, 58–63. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fasse, L.; Flahault, C.; Vioulac, C.; Lamore, K.; Van Wersch, A.; Quintard, B.; Untas, A. The decision-making process for breast reconstruction after cancer surgery: Representations of heterosexual couples in long-standing relationships. Br. J. Health Psychol. 2017, 22, 254–269. [Google Scholar] [CrossRef] [Scilit]
- Gray, R.E.; Fitch, M.I.; Phillips, C.; Labrecque, M.; Klotz, L. Presurgery experiences of prostate cancer patients and their spouses. Cancer Pract. 1999, 7, 130–135. [Google Scholar] [CrossRef] [Scilit]
- Lamore, K.; Vioulac, C.; Fasse, L.; Flahault, C.; Quintard, B.; Untas, A. Couples’ Experience of the Decision-Making Process in Breast Reconstruction after Breast Cancer: A Lexical Analysis of Their Discourse. Cancer Nurs. 2020, 43, 384–395. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Le, Y.-C.L.; McFall, S.L.; Byrd, T.L.; Volk, R.J.; Cantor, S.B.; Kuban, D.A.; Mullen, P.D. Is “Active Surveillance” an Acceptable Alternative?: A Qualitative Study of Couples’ Decision Making about Early-Stage, Localized Prostate Cancer. Narrat. Inq. Bioeth. 2016, 6, 51–61. [Google Scholar] [CrossRef] [Scilit]
- Loaring, J.M.; Larkin, M.; Shaw, R.; Flowers, P. Renegotiating sexual intimacy in the context of altered embodiment: The experiences of women with breast cancer and their male partners following mastectomy and reconstruction. Health Psychol. 2015, 34, 426–436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maliski, S.L.; Heilemann, M.V.; McCorkle, R. From “Death Sentence” to “Good Cancer”: Couples’ Transformation of a Prostate Cancer Diagnosis. Nurs. Res. 2002, 51, 391–397. [Google Scholar] [CrossRef] [Scilit]
- Nelson, K.; Bennett, P.; Rance, J. The experiences of giving and receiving social support for men with localised prostate cancer and their partners. Ecancermedicalscience 2019, 13, 989. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- O’Callaghan, C.; Dryden, T.; Hyatt, A.; Brooker, J.; Burney, S.; Wootten, A.C.; White, A.; Frydenberg, M.; Murphy, D.; Williams, S.; et al. “What is this active surveillance thing?” Men’s and partners’ reactions to treatment decision making for prostate cancer when active surveillance is the recommended treatment option. Psychooncology 2014, 23, 1391–1398. [Google Scholar] [CrossRef] [Scilit]
- Rim, S.H. Considering racial and ethnic preferences in communication and interactions among the patient, family member, and physician following diagnosis of localized prostate cancer: Study of a US population. Int. J. Gen. Med. 2011, 4, 481–486. [Google Scholar] [CrossRef] [Scilit]
- Al-Bahri, A.; Al-Moundhri, M.; Al-Mandhari, Z.; Al-Azri, M. Role of the family in Treatment Decision-Making process for Omani women diagnosed with breast cancer. Patient Educ. Couns. 2019, 102, 352–359. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cincidda, C.; Pizzoli, S.F.M.; Oliveri, S.; Pravettoni, G. Regulation strategies during COVID-19 quarantine: The mediating effect of worry on the links between coping strategies and anxiety. Eur. Rev. Appl. Psychol. 2021, 72, 100671. [Google Scholar] [CrossRef] [Scilit]
- Ongaro, G.; Cincidda, C.; Sebri, V.; Savioni, L.; Triberti, S.; Ferrucci, R.; Poletti, B.; Dell’Osso, B.; Pravettoni, G. A 6-Month Follow-Up Study on Worry and Its Impact on Well-Being During the First Wave of COVID-19 Pandemic in an Italian Sample. Front. Psychol. 2021, 12, 4609. [Google Scholar] [CrossRef] [Scilit]



Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).