1. Introduction
Anxiety symptoms among school-aged children have gained increasing clinical and educational attention over the past two decades [
1,
2]. Rising academic pressure, social expectations, and changes in family environments place many children at risk of experiencing persistent worry, tension, and physiological symptoms [
3,
4]. These symptoms can interfere with classroom performance, participation in group activities, and long-term emotional development [
5,
6]. When left unrecognized, childhood anxiety may progress to more severe difficulties during adolescence and adulthood, including avoidance behavior, reduced academic achievement, and heightened vulnerability to later mental health concerns [
7,
8]. Early identification is therefore an essential step in providing guidance, counselling, and structured support to children who may be struggling [
9,
10].
Reliable screening tools allow teachers, counsellors, and clinicians to recognize anxiety symptoms early and with greater accuracy [
11,
12]. Although several instruments exist for assessing emotional difficulties in children, not all of them perform equally well across cultural, linguistic, and regional backgrounds [
13,
14]. Measures developed and tested predominantly in Western populations may not automatically retain the same performance in other regions, as social norms, communication styles, and response patterns can differ substantially [
13,
15]. This highlights the importance of examining how a scale behaves in each new setting where it is used, especially when screening results will inform decisions about referral, follow-up assessment, or structured interventions.
The Revised Children’s Manifest Anxiety Scale-Second Edition (RCMAS-2) is among the most frequently used instruments for assessing anxiety in children aged six to nineteen years [
16,
17]. It offers a straightforward format, relies on simple self-report responses, and covers several domains that are commonly linked to anxiety during childhood—worry, physical signs of uneasiness, and concerns involving peer or social judgement [
16,
18]. Additionally, the measure includes built-in validity indicators that help flag inconsistent responding or attempts to present oneself more favorably, which strengthens its usefulness in school settings where children may be hesitant to disclose emotional difficulties [
18].
Despite its extensive use in other countries, there is very limited information on how the RCMAS-2 performs among school-going children in India [
3,
16]. Earlier Indian studies have primarily employed the original RCMAS rather than the updated RCMAS-2, reporting elevated anxiety symptoms in school samples and highlighting the need for culturally appropriate screening tools [
3,
19]. Cultural background, everyday stressors, and academic environments in India differ markedly from those in Western countries where the scale was originally tested [
13,
14]. For instance, expectations related to scholastic excellence, family involvement in educational decisions, and peer competition may influence how Indian children interpret and respond to items about worry or physical tension [
3]. Without local validation, there remains uncertainty about how well the tool identifies children who genuinely experience elevated anxiety and how accurate its recommended cut-off scores are for this population [
13,
17]. A systematic evaluation of the revised edition, including its validity indicators and updated factor structure, has not yet been reported in Indian settings. Establishing psychometric evidence for the RCMAS-2 is particularly important before applying publisher-recommended cut-offs to local school populations.
The present study addresses this important gap by evaluating the performance of RCMAS-2 scores in a large sample of school-going students from India. This dataset provides an opportunity to examine how the scale functions after excluding responses that show signs of poor accuracy based on the defensiveness validity indicator. Screening tools must demonstrate clear performance even after such exclusions, as response bias can otherwise distort sensitivity, specificity, and overall detection efficiency. By focusing on a refined sample, the study aims to present an accurate picture of how the scale behaves when used with Indian students.
Given the lack of prior research on this instrument in the Indian context, this study was conducted in English-medium private schools in Sikkim. Establishing how RCMAS-2 performs in this population not only helps strengthen local clinical practice and school-based screening but also contributes to the broader understanding of how anxiety measures work across diverse cultures. Having a reliable tool that responds well to local conditions can support early identification, guide counselling efforts, and improve access to help for children who may otherwise remain unnoticed. By presenting these findings, the study aims to support the use of RCMAS-2 as a dependable screening option for childhood anxiety within the Indian context, while also offering a foundation for further research that may explore item-level patterns, cultural influences, or longitudinal tracking of emotional health in children.
2. Method
2.1. Participants
The study was conducted in English medium private schools across all four districts of Sikkim, India, between March 2018 to November 2019. 1001 Children from classes 2–5 (age range 7–10 years) were recruited through multistage cluster sampling. A complete list of private schools registered with the State Education Department was obtained prior to recruitment. Using district-wise stratification, 30 schools were randomly selected across Sikkim (East = 12, West = 7, North = 5, South = 6). Eleven schools were unable to participate due to administrative and scheduling constraints, including time limitations and withdrawal at the institutional level. Consequently, 19 schools were included in the final study (East = 7, West = 6, North = 3, South = 3). Schools were selected to ensure that participating children had adequate English proficiency to comprehend the RCMAS-2 item content as administered. A linguistically homogeneous administration setting was maintained to reduce variability arising from translation or multilingual interpretation and to support consistency in evaluating the psychometric structure of the instrument during the initial validation phase.
Parental consent was obtained for approximately 65% of eligible students (N = 3250). Among those who consented, nearly 40% could not be assessed due to school-level attrition or student absence on the day of data collection. This resulted in 1812 children completing the administered assessments. Complete and usable data across all study variables were available for 1001 participants, who formed the initial analytic sample for the present psychometric evaluation. 117 Children were excluded from the psychometry study either due to a defensiveness score > 7 (103) or inconsistent responding > 6 (14). The final sample consisted of 884 children (463 boys, 421 girls; Mean age = 8.5 years, SD = 1.18). Representation by district was balanced (East District: 32.6%, West District: 23.5%, North District: 21.8%, South District: 22%). All the children were from grades 2–5, reflecting the RCMAS-2’s primary target age range.
2.2. Revised Children’s Manifest Anxiety Scale-Second Edition (RCMAS-2)
The RCMAS-2 is a 49-item self-report questionnaire designed to assess anxiety in children and adolescents aged 6–19 years. Items are answered “Yes” (1) or “No” (0). It yields a Total Anxiety score (40 items), three anxiety subscales (Physiological Anxiety, 12 items; Worry, 16, items; Social Anxiety, 12 items), a 9-item Defensiveness scale, and a brief Inconsistent Responding index [
19]. Raw scores are converted to age- and gender-normed T-scores (M = 50, SD = 10) using U.S. norms. The manual reports internal consistency coefficients of 0.81–0.92 and test–retest reliabilities of 0.76–0.85. Permission for research use was obtained from Western Psychological Services (WPS, License: WPS-001532).
2.3. Beck Anxiety Inventory (BAI)
The BAI is a widely used 21-item adult self-report measure of anxiety severity. Each item is rated on a 0–3 scale (“Not at all” to “Severely”). Total scores range from 0 to 63. Although developed for adults, it was included to examine convergent validity and to test the hypothesis that an adult-oriented instrument would perform poorly in children. The Indian version has shown good reliability (α = 0.91) in previous adolescent samples. BAI was included as an exploratory comparator to examine the extent of score overlap between the RCMAS-2 and a widely used anxiety symptom measure primarily designed for adults. Given the developmental differences in anxiety expression and item content between adult and child populations, the BAI should be considered a suboptimal convergent validity reference for children aged 7–10 years.
2.4. Ethical Considerations
The study was reviewed, and ethical clearance was obtained from the Institutional Ethics Committee and the Institutional Review Committee of Sikkim Manipal Institute of Medical Sciences, Sikkim Manipal University (Approval code: SMIMS/IEC/2021-61; Approval date: 31 August 2021). Written consent from the Head of the Institutes was obtained from the schools which consented to participate in the study. Written Informed consent was also obtained from the participant’s parent/guardian and verbal assent from the children.
2.5. Data Analysis
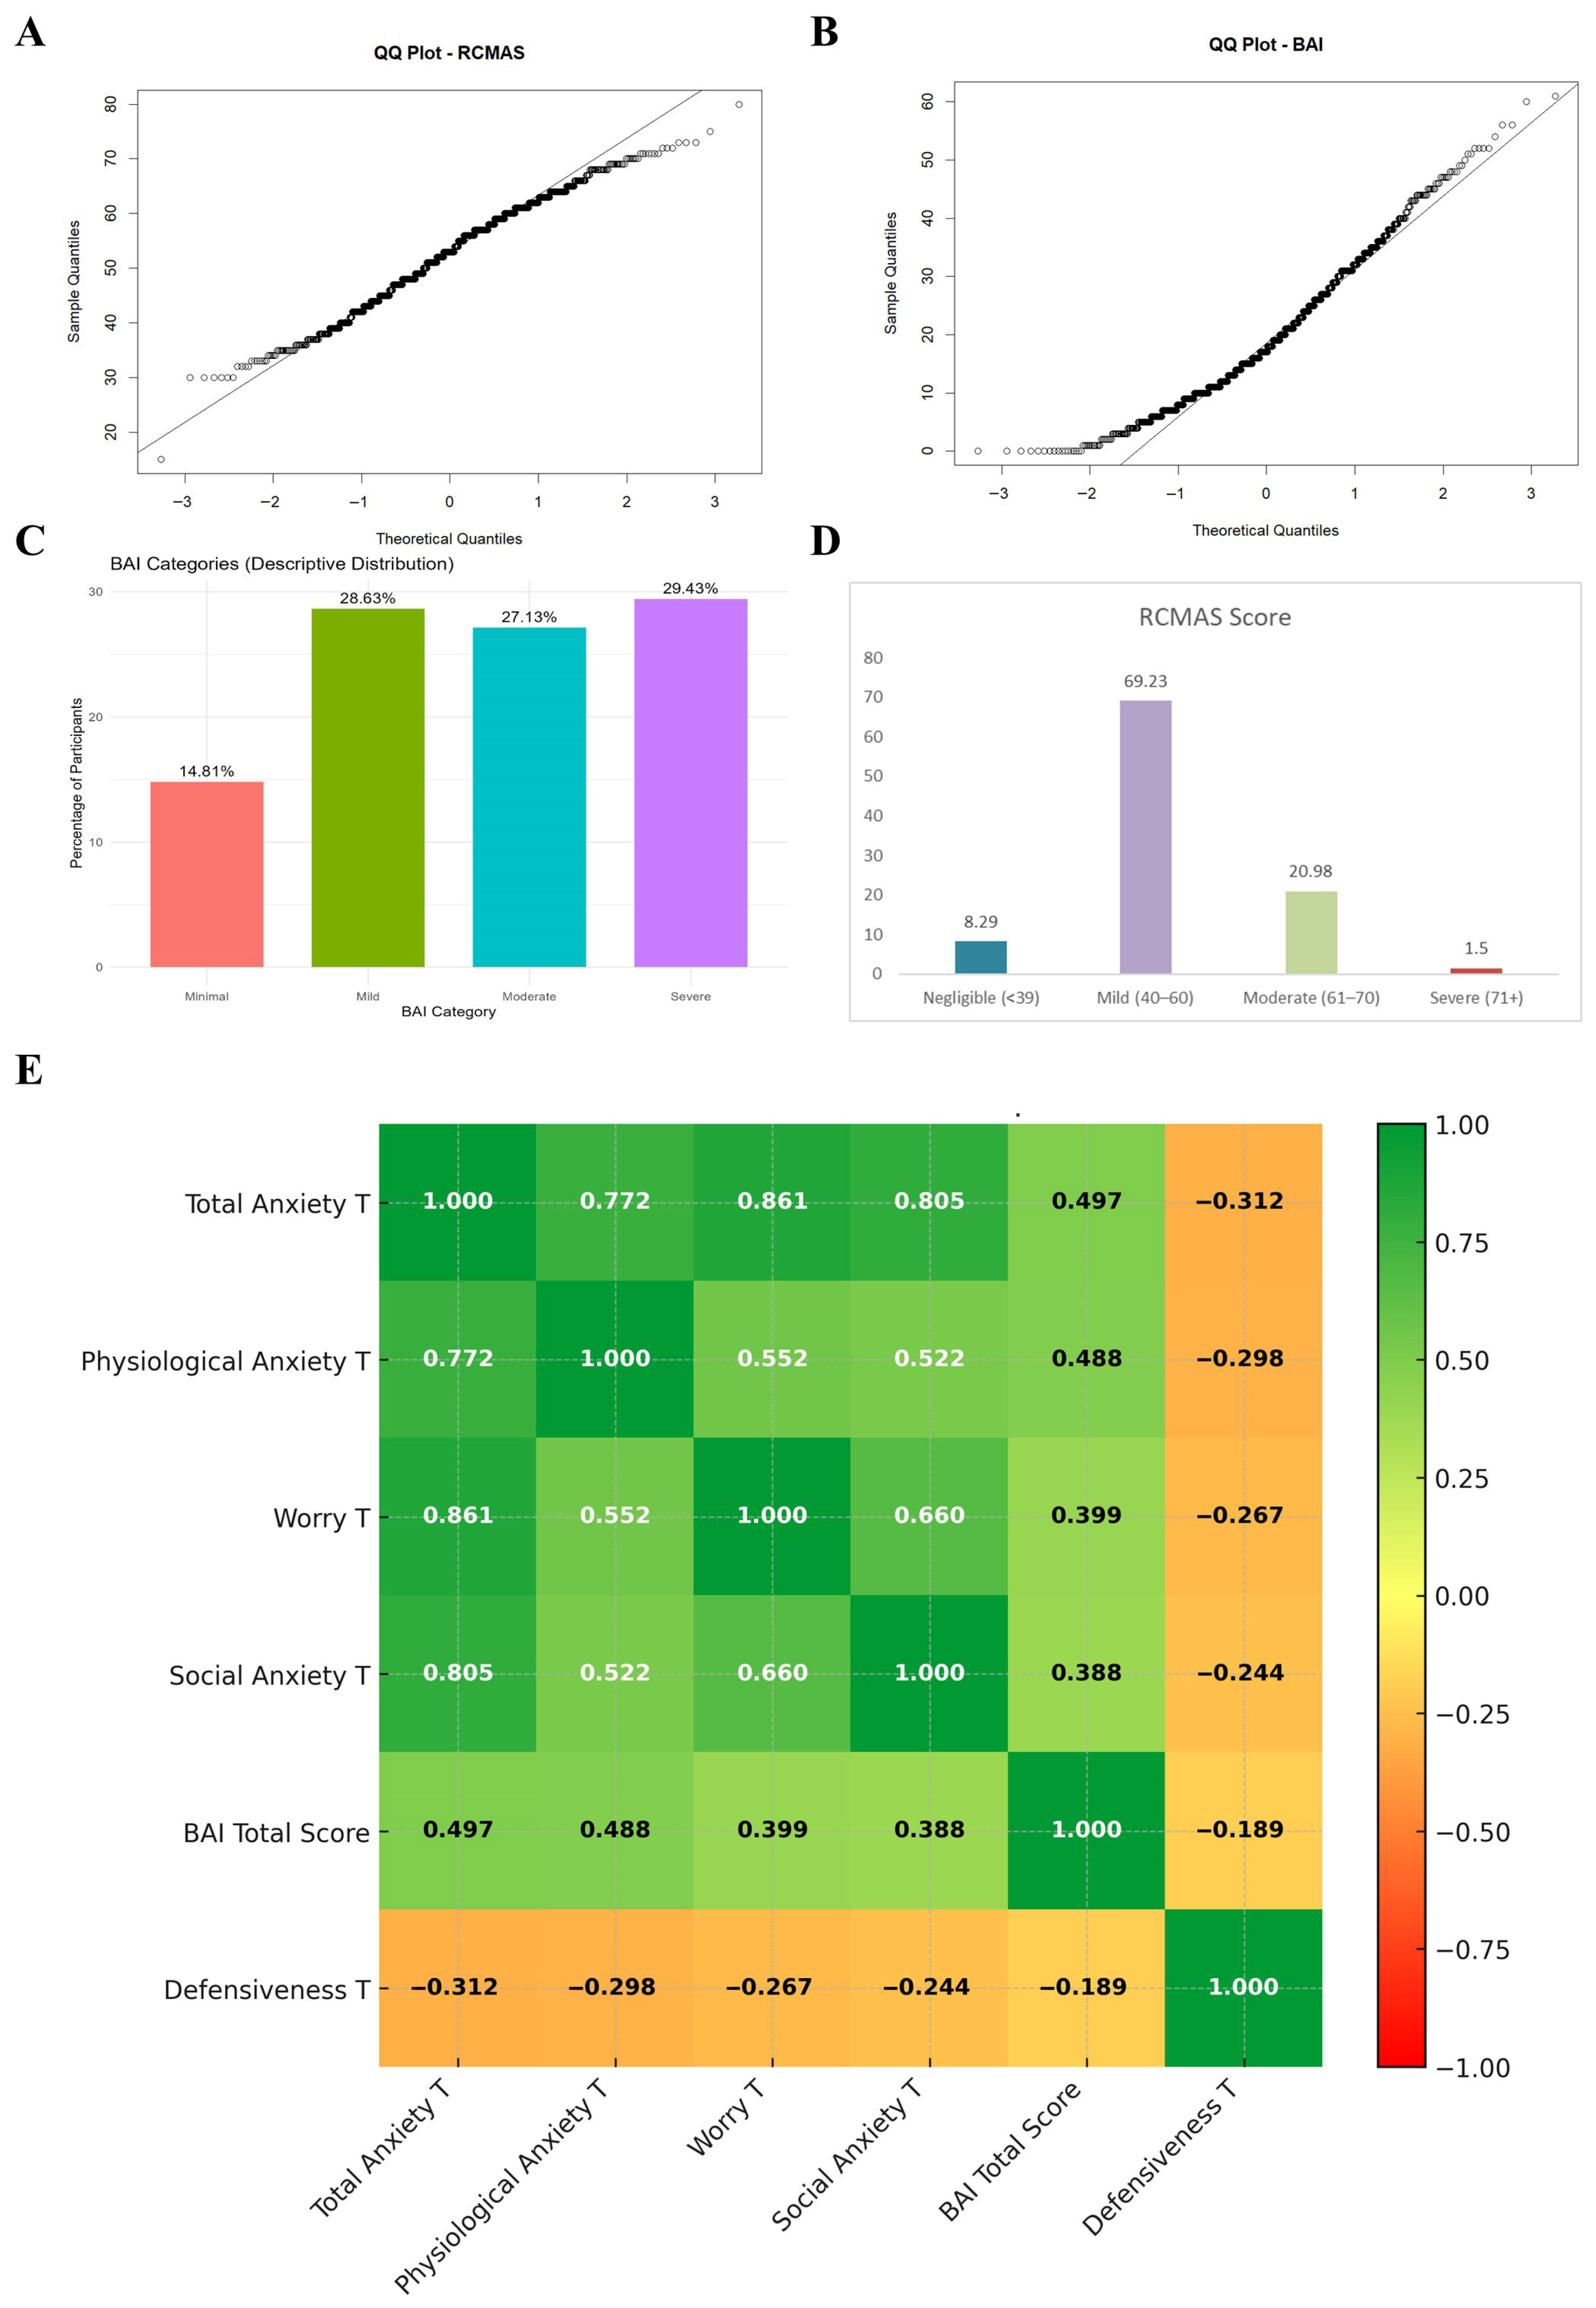
Data were entered into Microsoft Excel 365 and cleaned for outliers and missing values (less than 0.5% missing across all variables, handled by mean imputation for subscale totals only). All the statistical analyses have been performed in RStudio (version 2026.01.0+392; R version 4.5.2). Descriptive statistics (means, standard deviations, ranges) were computed for all RCMAS-2 T-scores and BAI total scores. Normality was assessed using Q-Q plots. Independent t-tests examined gender differences, and age-group differences (7–8 vs. 9–10 years) were tested with independent t-tests and Cohen’s d effect sizes. Principal component analysis (PCA) with varimax rotation was conducted on the four RCMAS-2 T-score indices to explore structural coherence. Pearson correlations assessed convergent validity and subscale interrelationships. Receiver operating characteristic (ROC) analyses were performed using the established RCMAS-2 Total Anxiety cut-off of T > 60 as an operational threshold for elevated anxiety (not a clinical gold standard). Area under the curve (AUC), 95% confidence intervals, sensitivity, specificity, and Youden’s index were calculated for the BAI total score only, to evaluate its ability to classify children relative to this RCMAS-2-defined threshold.
2.6. Confirmatory Factor Analyses (CFAs)
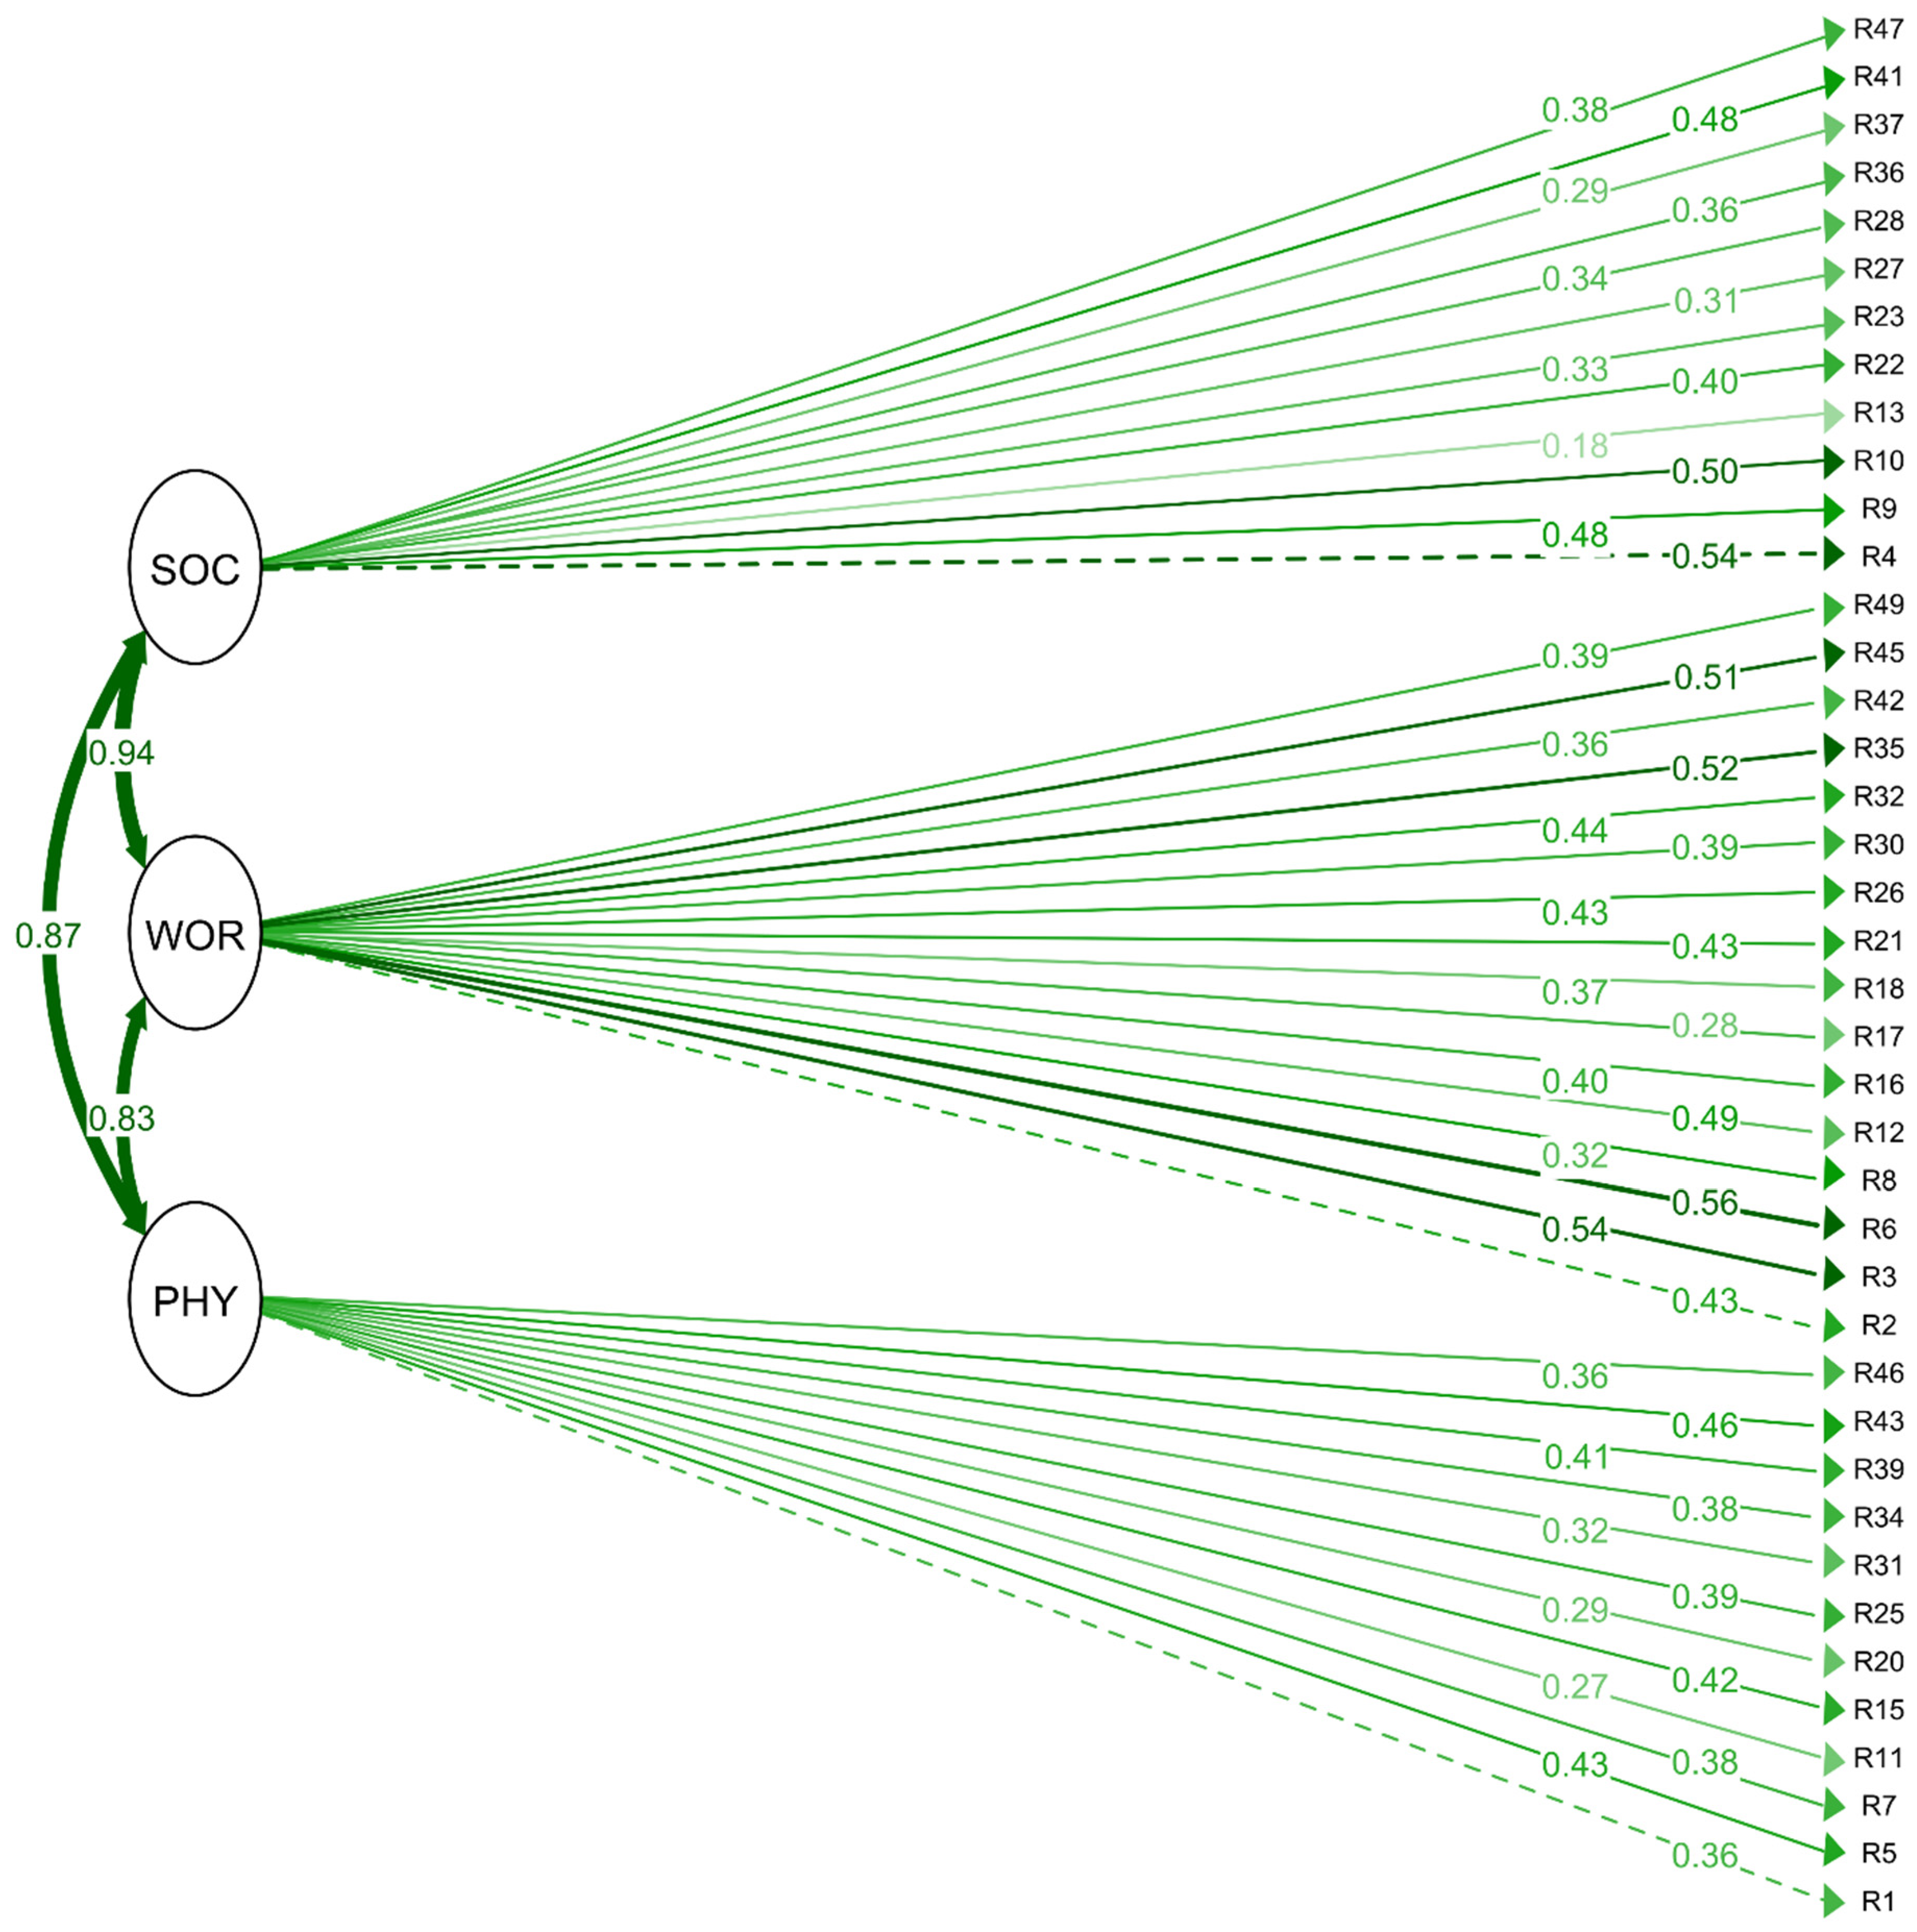
Item-level CFA models were estimated for the 884 responses using the robust weighted least squares estimator (WLSMV), which is appropriate for ordinal response data. Each item was specified to load on its theoretically assigned factor as defined in the RCMAS-2 manual, with cross-loadings constrained to zero. Factor variances were fixed to 1 for identification, and latent factors were allowed to correlate. Model fit was evaluated using established indices (CFI, TLI, RMSEA, SRMR).
2.7. Item-Level Structural Analysis
Item-level structural estimates were examined to understand how each RCMAS-2 item contributed to its intended latent factor. Standardized regression coefficients (β), standard errors, and
p-values were extracted from the weighted least squares model using the fitted CFA object. Items were grouped according to their predefined subscales: Physiological (PHY), Worry (WOR), and Social Anxiety (SOC). Defensiveness items were not included in the regression model because they serve as validity indicators rather than markers of the latent construct. The analysis produced standardized coefficients and significance values for all items, along with latent factor correlations. The cleaned summary of these results is provided in the item-level regression table included in the
Supplementary Materials.
4. Discussion
This study provides the first comprehensive psychometric evaluation and normative data for the Revised Children’s Manifest Anxiety Scale-Second Edition (RCMAS-2) in an Indian population. The scale demonstrated strong internal consistency, structural validity, and expected subscale coherence within this population. Mean anxiety scores were mildly elevated relative to U.S. normative expectations, and a substantial proportion of children exceeded the publisher-recommended screening threshold, highlighting the importance of school-based mental health attention in similar educational settings [
20].
The internal structure and subscale intercorrelations observed here closely mirror those reported in the RCMAS-2 manual and subsequent international validations. Reynolds and Richmond (1985) documented subscale intercorrelations of 0.52–0.68 and subscale–total correlations of 0.75–0.86 in the U.S. normative sample, values nearly identical to the present findings (0.52–0.66 and 0.77–0.86, respectively) [
20]. Similar patterns have been replicated in diverse contexts: Italian adolescents [
12] and Iranian school samples [
24], all reporting strong unidimensionality of the Total Anxiety score and high subscale coherence. The scree plot and one-factor solution in the current study (
Figure S1 further confirm that the RCMAS-2 functions as intended in Indian children, despite linguistic and cultural differences. Convergent validity with other anxiety measures has consistently been moderate-to-strong across cultures. The
r = 0.498 correlation with the BAI observed here is comparable to correlations of 0.45–0.62 reported between the RCMAS-2 and the Screen for Child Anxiety Related Emotional Disorders (SCARED) in U.S. and European studies [
12,
25]. The notably stronger association between the Physiological Anxiety subscale and the BAI (
r = 0.492) reflects the BAI’s somatic emphasis and aligns with findings from adult and adolescent samples using similar measures [
26].
Although this is the first RCMAS-2 study in India, several investigators have employed the original 37-item RCMAS. Mean Total Anxiety scores in Indian school samples using the RCMAS have ranged from 13.2 to 16.8 raw score points [
27,
28,
29], consistently higher than U.S. norms (approximately 11–12). Converting the present RCMAS-2 raw Total Anxiety score (M ≈ 19–20 in the elevated subsample) to the older metric suggests continuity with this pattern of heightened anxiety reporting in Indian children.
The consistently higher anxiety levels observed across Indian studies, now confirmed with the updated RCMAS-2, challenge the notion that anxiety is universally lower in collectivist cultures. Academic pressure, parental expectations, rapid sociocultural change, and exposure to familial stress have been proposed as contributing factors [
27,
28]. The particularly elevated Worry subscale in the present sample (M = 54.25) aligns with qualitative reports of pervasive performance anxiety and fear of failure among Indian schoolchildren [
28]. The absence of significant gender differences replicates most Indian RCMAS studies and contrasts with Western samples, where girls typically score higher, suggesting culturally moderated gender expression of anxiety [
14,
30].
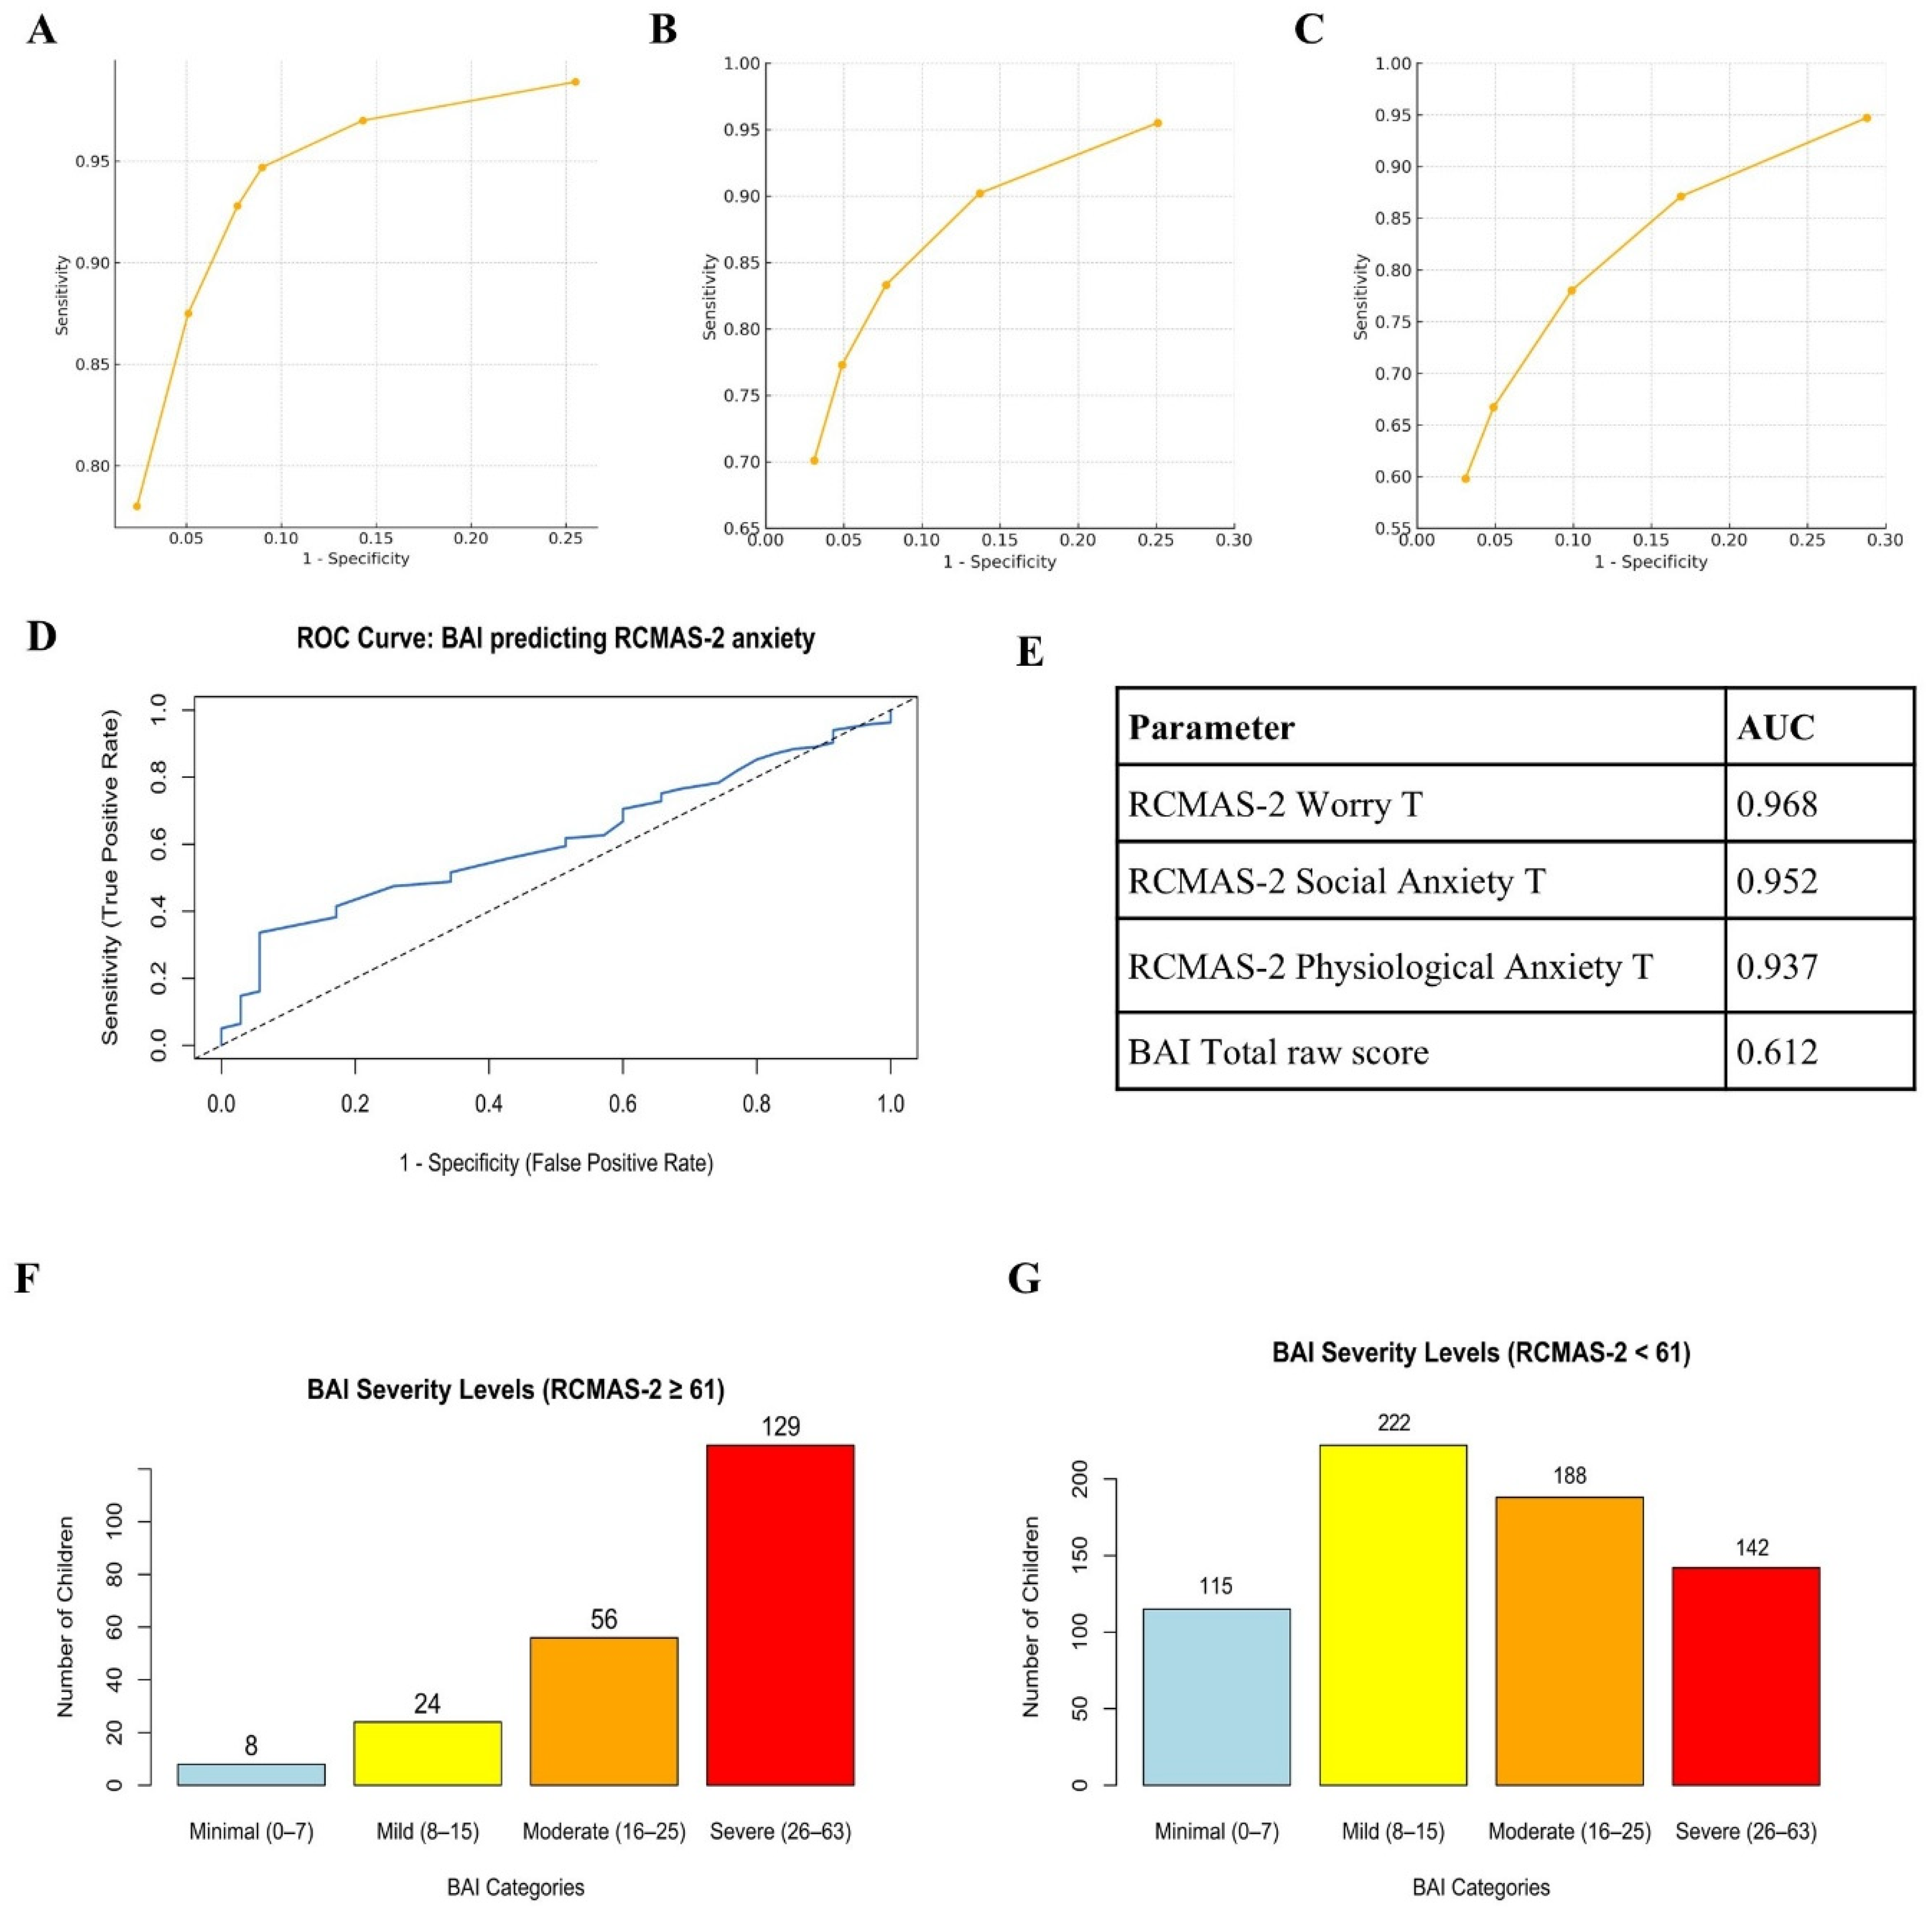
The ROC analyses provide striking empirical evidence that the RCMAS-2 demonstrated stronger alignment with childhood anxiety symptom dimensions than the adult-oriented BAI (AUC 0.994 vs. 0.786). Even at its optimal cut-off, the BAI misclassified approximately 30% of clinically anxious children. This finding underscores the developmental inappropriateness of adult anxiety instruments for pre-adolescents: many BAI items (e.g., “fear of dying,” “fear of losing control”) are cognitively and experientially alien to young children. The near-perfect discrimination of the RCMAS-2 Total score validates the publisher’s T ≥ 60 cut-off in an entirely new cultural context and supports its use as a gold-standard screening tool in Indian schools.
Confirmatory factor analysis further supported the structural validity of the RCMAS-2 in this Indian sample, with the higher-order model (three anxiety subscales loading onto a general Anxiety factor) showing excellent fit (CFI = 0.99, RMSEA = 0.064) and outperforming the strict one-factor solution [
17,
20]. The Physiological, Worry/Oversensitivity, and Social Concerns/Concentration subscales loaded strongly on the general factor (λ = 0.56–0.81), whereas Defensiveness showed a near-zero loading (λ = 0.04), confirming its role as an independent validity indicator rather than part of the core anxiety construct [
16]. This pattern mirrors findings from other non-Western samples and reinforces the dominance of a single broad anxiety dimension in Indian children. These results provide strong evidence that the RCMAS-2 Total Anxiety score is psychometrically meaningful and culturally appropriate for screening in this population. Item-level estimates further supported the intended RCMAS-2 structure in this sample. Most items showed meaningful loadings on their respective factors, with Worry and Social Concerns items demonstrating particularly strong alignment. Physiological items displayed moderate contributions, consistent with the somatic dimension being less prominent in this age group. A small number of items (R1, R2, and R4) showed weaker or nonsignificant coefficients, reflecting limited variability in endorsement rather than substantive problems with the scale. Overall, the item-level pattern indicates that the RCMAS-2 items function appropriately in this population and provides additional support for the scale’s structural validity.
The present findings establish the RCMAS-2 as a psychometrically robust, culturally transportable instrument for assessing anxiety in Indian children aged 7–10 years. The preliminary local norms and high prevalence of clinically significant scores highlight an urgent need for school-based mental health screening programs, particularly in high-performing academic environments. Given the better classification accuracy demonstrated here, clinicians and researchers in India should preferentially adopt the RCMAS-2 over adult measures such as the BAI when evaluating childhood anxiety.
5. Limitations
Although the study contributes significantly to the existing knowledge, several limitations still remain that need to be addressed in the future. First, the ROC analysis used an operational RCMAS-2 threshold rather than a clinical gold standard. Second, the study relied on self-report questionnaires without multi-informant data or clinical benchmarks. Third, the sample was drawn from private schools in one state (Sikkim), limiting generalizability to government/public schools, boarding schools or to other regions/states. Finally, the cross-sectional design precludes causal inferences. Fourth, ROC analyses are not benchmarked against clinical interviews and do not support disorder-level diagnostic inference. The inclusion of the BAI was primarily driven by feasibility and instrument availability during data collection, rather than its suitability as an optimal child anxiety comparator. Because the BAI was developed for adult populations, its items may not fully capture developmentally appropriate anxiety experiences in younger children. Therefore, results involving the BAI should be interpreted cautiously and viewed as preliminary evidence of partial score correspondence rather than strong convergent validation. Elevated anxiety scores observed in this sample should be interpreted within the socioeconomic context of private school attendance, where academic expectations and performance-related pressures may differ from those experienced in lower-resource educational settings. Future research should address these by incorporating diagnostic interviews, diverse samples, and longitudinal follow-up. Validation research in Indian child populations should incorporate developmentally appropriate anxiety instruments, such as the Screen for Child Anxiety Related Emotional Disorders (SCARED), the Spence Children’s Anxiety Scale (SCAS), or the Revised Child Anxiety and Depression Scale (RCADS), to provide stronger convergent validity evidence and more clinically interpretable comparisons.