


Abstract
Anaplastic lymphoma kinase (ALK) tyrosine kinase inhibitors (TKIs) have dramatically transformed the clinical management of ALK-rearranged non-small cell lung cancer (NSCLC). Successive generations of ALK inhibitors have been developed to overcome resistance mediated by kinase domain mutations, culminating in the third-generation inhibitor lorlatinib. Despite these advances, resistance remains inevitable, and durable disease control is rarely achieved. While resistance driven by single ALK mutations has been extensively characterized and structurally classified, the emergence of compound ALK mutations under sequential TKI therapy represents a qualitatively distinct and insufficiently conceptualized resistance state. This issue is becoming more complex as lorlatinib is increasingly used in the first-line setting, where resistance may arise from an ALK TKI-naïve background rather than from tumors already shaped by sequential ALK inhibition. In this review, we propose a unified framework that integrates structural single ALK resistance mutations (Types 1–3) with compound ALK mutations (Type 4) as a distinct evolutionary entity. We argue that compound mutations mark a critical inflection point at which ALK dependency reaches its functional limit, explaining the failure of even highly potent inhibitors such as lorlatinib. Importantly, we discuss how certain compound mutations paradoxically restore sensitivity to earlier-generation TKIs, highlighting the value of structural interpretation over linear drug sequencing. Finally, we discuss the transition toward ALK-independent resistance and future strategies incorporating dynamic molecular monitoring and structure-agnostic therapies. This framework may help clinicians interpret resistance mechanisms and guide rational treatment selection in daily practice.
1. Introduction
Chromosomal rearrangements involving anaplastic lymphoma kinase (ALK), most commonly the echinoderm microtubule-associated protein-like 4 (EML4)–ALK fusion, were first identified in non-small cell lung cancer (NSCLC) in 2007 and established ALK as a potent oncogenic driver [1]. ALK rearrangements occur in approximately 3–8% of NSCLC cases and define a distinct molecular subset that is highly sensitive to targeted kinase inhibition [2,3]. Six ALK tyrosine kinase inhibitors (TKIs) are now approved by the U.S. Food and Drug Administration across three generations—crizotinib, ceritinib, alectinib, brigatinib, ensartinib, and lorlatinib—underscoring the substantial clinical impact of ALK-directed therapy [4,5,6,7,8,9,10,11,12].
First-generation inhibition with crizotinib demonstrated substantial clinical activity, establishing oncogenic ALK signaling as a dominant and actionable therapeutic target [13]. Subsequent generations of ALK TKIs, including ceritinib, alectinib, brigatinib, and ensartinib, were rationally engineered to inhibit acquired resistance mutations that emerged under therapeutic pressure, resulting in improved progression-free survival and more durable disease control [7,11]. Lorlatinib, a third-generation ALK inhibitor, was specifically engineered to inhibit a broad spectrum of known resistance mutations, including solvent-front and gatekeeper alterations that limited the efficacy of earlier agents [14]. Lorlatinib has shown robust intracranial activity and has become a cornerstone of treatment in both first-line and later-line settings [9,15].
Nevertheless, even lorlatinib ultimately fails in the majority of patients, underscoring the persistent challenge of acquired resistance. Traditionally, resistance to ALK TKIs has been conceptualized as a problem of single kinase domain mutations. Structural analyses have provided detailed insights into how individual amino acid substitutions disrupt drug binding and how specific inhibitors can be designed to accommodate these changes [14,16]. This paradigm has been highly successful in guiding sequential therapy and drug development. However, the increasing use of sequential ALK-TKI therapy has revealed a growing population of tumors harboring multiple ALK mutations acquired over time [17]. These compound mutations cannot be explained by structural models derived from single substitutions and frequently coincide with failure of even the most potent inhibitors, suggesting a fundamentally distinct resistance state [18,19]. Importantly, the accumulation of multiple mutations is not merely a quantitative increase in resistance but reflects a qualitative shift in kinase structure, conformational dynamics, and drug susceptibility.
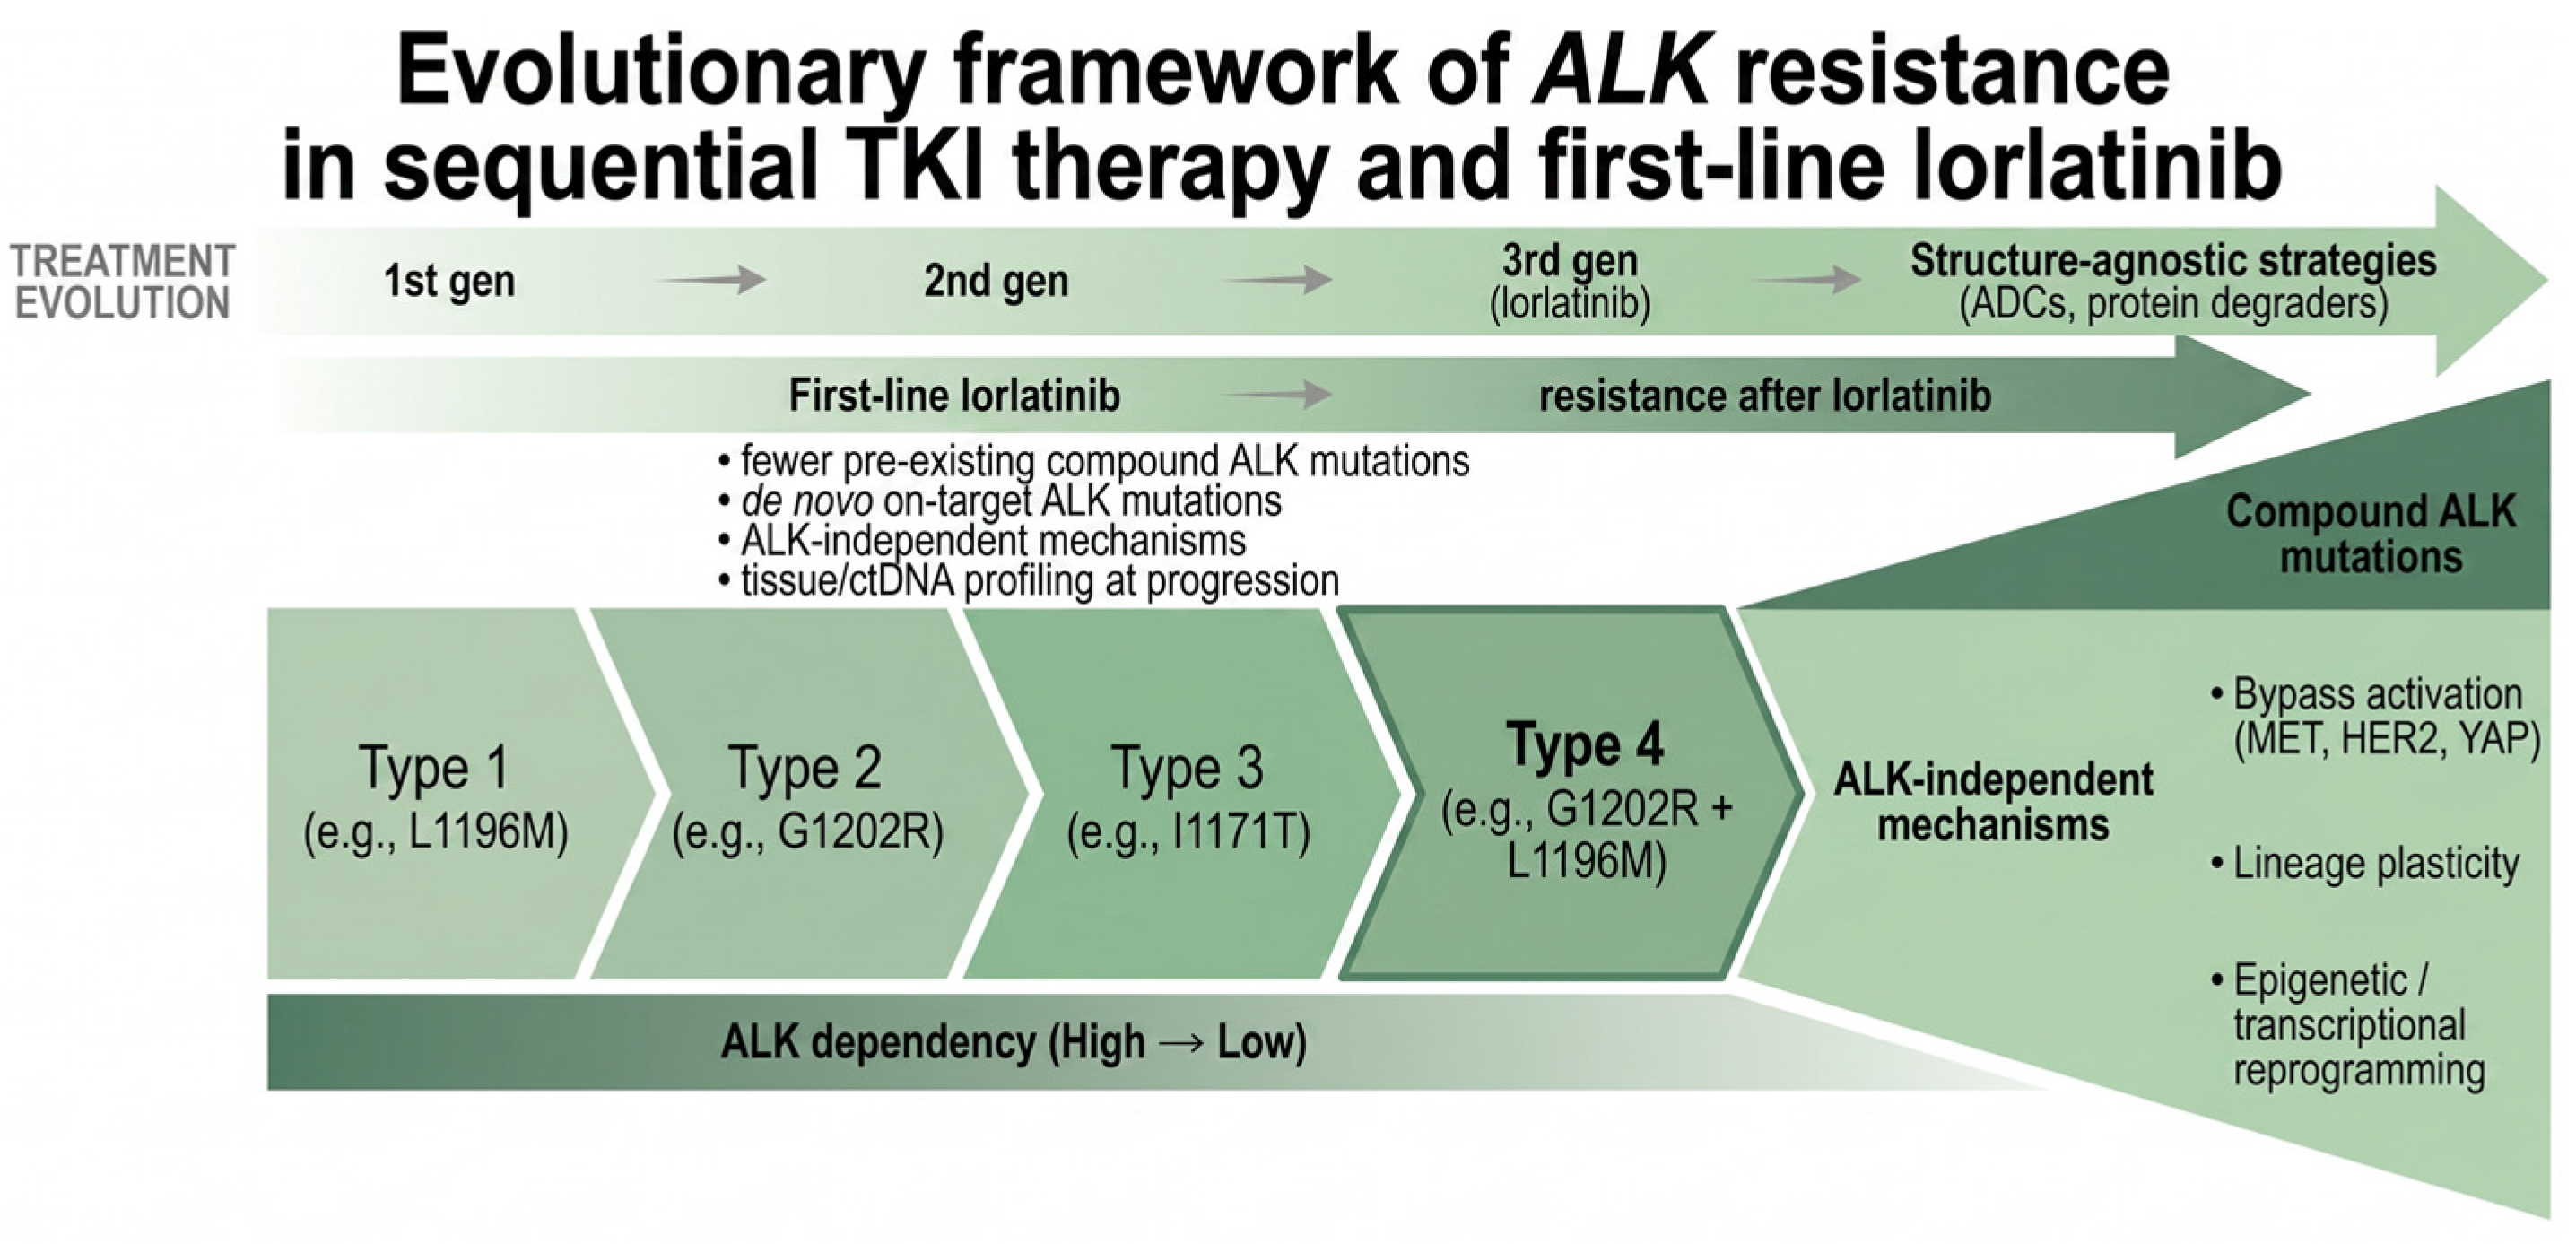
In this review, we propose a unified conceptual framework that distinguishes structural single ALK mutations (Types 1–3) from compound mutations (Type 4) and places them along an evolutionary trajectory shaped by therapeutic pressure. We further argue that compound mutations represent the final ALK-dependent resistance state, beyond which tumors may transition toward ALK-independent survival mechanisms. By integrating structural biology, clinical observations, and emerging diagnostic approaches, this framework provides a coherent lens through which to understand lorlatinib failure and to guide future therapeutic strategies, as summarized in Figure 1.
Figure 1.
Schematic overview of ALK resistance evolution under sequential ALK-TKI therapy and first-line lorlatinib. Single ALK resistance mutations (Types 1–3) arise at distinct structural regions of the kinase domain, including gatekeeper, solvent-front, and kinase-core regions, and generally preserve ALK dependency. Under sequential ALK-TKI pressure, tumors may accumulate compound ALK mutations (Type 4), leading to high-level resistance and reduced sensitivity to next-generation inhibitors. In the first-line lorlatinib setting, resistance may emerge from an ALK TKI-naïve background with fewer pre-existing compound mutations, and may involve de novo on-target ALK mutations, ALK-independent mechanisms, or both. Tissue biopsy and/or ctDNA profiling at progression is therefore important for distinguishing ALK-dependent from ALK-independent resistance and guiding subsequent treatment strategies.
Given the rapid transition of lorlatinib from a later-line treatment to a first-line therapeutic option, a focused review integrating compound ALK mutations, lorlatinib resistance, and evolving treatment sequencing is timely and clinically relevant.
2. Structural Classification of Single ALK Resistance Mutations (Types 1–3)
Single ALK domain mutations remain the most extensively studied mechanism of resistance to ALK tyrosine kinase inhibitors (TKIs) [20]. Representative mutations for each structural class are summarized in Table 1, which provides a comprehensive catalog of reported single resistance mutations and their clinical context. These mutations typically arise under selective pressure from first- and second-generation inhibitors and affect drug binding through defined structural mechanisms [21]. Structural analyses have enabled the classification of these mutations based on their location within the kinase domain and their functional consequences [14].
Type 1 mutations include alterations that directly interfere with inhibitor binding at the ATP-binding pocket, most commonly gatekeeper substitutions such as L1196M and G1269A (Table 1) [20,22]. These substitutions reduce inhibitor affinity while preserving kinase activity, leading to resistance that can often be overcome by next-generation inhibitors with modified binding modes [21]. Type 2 mutations encompass solvent-front alterations, exemplified by G1202R, the most frequently reported single mutation conferring broad cross-resistance (Table 1) [23,24]. These mutations pose particular challenges for drug design due to steric constraints but have been successfully targeted by structurally optimized inhibitors, including lorlatinib [16]. Type 3 mutations involve residues that influence the conformational equilibrium of the kinase, such as those affecting the αC-helix or activation loop, including I1171T/N/S, V1180L, and L1196Q (Table 1) [18,25,26]. By stabilizing active or inactive conformations, these mutations indirectly reduce inhibitor efficacy [27].
Importantly, tumors harboring Types 1–3 mutations typically remain highly dependent on oncogenic ALK signaling, representing a shared functional feature across these structural classes. These mutations are also not spatially isolated within the kinase domain [22]. Residues classified as gatekeeper, solvent-front, or conformational regulators partially overlap and collectively shape inhibitor accommodation. This spatial convergence provides a mechanistic basis for the qualitative resistance shift observed when multiple mutations co-occur. This preserved ALK dependency explains the clinical efficacy of sequential ALK-TKI therapy, as resistance driven by single kinase domain mutations can frequently be suppressed by next-generation inhibitors with broader potency and structural coverage. However, this paradigm becomes increasingly fragile as therapeutic pressure intensifies and additional mutations accumulate.
Table 1.
Structural classification of single ALK resistance mutations (Types 1–3). Representative single kinase domain mutations are grouped by structural mechanism (gatekeeper/ATP-binding pocket, solvent-front, or kinase core residues), with prior ALK-TKI exposure and detection methods indicated.
3. Compound ALK Mutations as a Distinct Resistance Entity (Type 4)
3.1. Definition and Evolutionary Emergence
Compound ALK mutations are defined by the presence of two or more ALK domain mutations within the same tumor. Reported compound mutation patterns and their clinical backgrounds are summarized in Table 2. However, the clinical impact of compound mutations is not determined solely by mutation number. Recurrent combinations affecting both steric hindrance and conformational flexibility are disproportionately associated with high-level lorlatinib resistance. By contrast, incidental co-occurrence of rare mutations may not uniformly confer functional failure. These mutations typically arise through stepwise accumulation during sequential exposure to multiple ALK inhibitors [17]. Unlike single mutations, compound mutations reflect prolonged and intense selective pressure exerted by successive therapies [18]. Importantly, the emergence of compound ALK mutations should not be viewed as a static extension of single-mutation resistance. Rather, sequential exposure to multiple generations of ALK tyrosine kinase inhibitors actively shapes the evolutionary trajectory of resistant clones. Each successive inhibitor imposes additional structural constraints on the kinase domain, progressively narrowing the mutational landscape and favoring the selection of compound mutations that can simultaneously accommodate multiple selective pressures. In this context, compound mutations represent an evolutionary endpoint of ALK-dependent resistance, arising through dynamic selection rather than random accumulation.
Table 2.
Reported compound ALK mutations (Type 4) and clinical context. Compound mutations (≥2 concurrent ALK alterations) with prior therapies, detection methods, and key references are summarized.
3.2. Recurrent Patterns and Clinical Detection
Analysis of reported clinical cases reveals recurrent combinations of ALK mutations, suggesting that compound mutations are shaped by non-random evolutionary constraints [18,28]. Certain combinations appear repeatedly across independent patients, indicating convergent evolutionary solutions to therapeutic pressure. Notably, many compound mutations have been identified through plasma circulating tumor DNA (ctDNA) analysis rather than tissue biopsy [17], reflecting the spatial and temporal heterogeneity of resistant clones. This observation supports the use of liquid biopsy as a complementary approach for capturing evolving ALK mutation diversity under treatment pressure.
3.3. Why Compound Mutations Defeat Next-Generation Inhibitors
Compound ALK mutations should not be viewed as a simple extension of single-mutation resistance. Single ALK mutations can often be interpreted through localized structural effects, such as altered inhibitor binding at the gatekeeper, solvent-front, or kinase-core regions. By contrast, when multiple mutations coexist within the same kinase domain, they may impose cooperative structural constraints across several functional regions, resulting in resistance profiles that cannot be predicted from the corresponding single mutations alone [18,24].
This distinction is particularly relevant for lorlatinib. Lorlatinib was designed as a macrocyclic ALK/ROS1 inhibitor with broad activity against many single ALK resistance mutations, including mutations that limit the efficacy of earlier-generation inhibitors [16]. Nevertheless, compound mutations selected after sequential ALK-TKI exposure can markedly reduce lorlatinib sensitivity [18]. For example, G1202R + L1196M combines a solvent-front alteration with a gatekeeper mutation, introducing simultaneous steric interference and altered kinase-domain accommodation. This dual structural constraint can reduce lorlatinib binding more substantially than either mutation alone [18].
Therefore, compound mutations represent a qualitatively different resistance state rather than a mere accumulation of single resistance events. Once the kinase domain has acquired multiple substitutions under sequential therapeutic pressure, conventional ALK inhibition may approach its structural and functional limit. Although direct evidence that compound ALK mutations create entirely new non-native biomolecular interactions remains limited, their cooperative structural effects may alter inhibitor binding, kinase conformation, and downstream pathway dependency. This provides the rationale for considering alternative strategies, including genotype-guided rechallenge in selected cases, rational combinations, and structure-agnostic approaches such as ADCs or protein degradation strategies.
3.4. Paradoxical Resensitization and Structural Vulnerabilities
Compound mutations do not necessarily represent a monotonic progression toward ever-greater drug resistance. The best-characterized example is the lorlatinib-emergent L1198F substitution, which impairs lorlatinib binding while paradoxically restoring sensitivity to crizotinib. In the index case reported by Shaw et al., crizotinib rechallenge produced marked tumor regression after lorlatinib resistance, providing direct clinical evidence of mutation-specific resensitization [30].
Although currently supported by limited clinical reports and retrospective molecular analyses, these findings suggest that some compound mutations may create new structural vulnerabilities even as they confer resistance to newer inhibitors. Systematic molecular monitoring may therefore help identify rare but actionable opportunities for genotype-directed drug rechallenge. At present, however, clinical evidence remains limited, and prospective validation is needed before such adaptive sequencing strategies can be broadly recommended [18,19,30].
4. Clinical Implications of Compound ALK Mutations
The emergence of compound ALK mutations has profound implications for clinical management. Sequential ALK-TKI therapy, while effective in earlier stages of disease, may inadvertently promote the accumulation of resistance mutations that ultimately exhaust the therapeutic space of ALK inhibition [17].
From a diagnostic perspective, the structural and clonal complexity of compound ALK mutations fundamentally challenges conventional tissue-based genotyping. Because compound mutations frequently arise from spatially and temporally heterogeneous resistant clones, plasma ctDNA-based next-generation sequencing is not merely complementary but essential for their reliable detection and longitudinal monitoring [17]. Tissue biopsy may capture only a limited clonal snapshot, whereas ctDNA more accurately reflects the evolving composite mutational landscape under sequential ALK-TKI pressure. For this reason, ctDNA-based monitoring has become an increasingly important component of longitudinal molecular surveillance in advanced ALK-positive NSCLC. However, liquid biopsy has inherent limitations. Tumors with isolated central nervous system progression may exhibit minimal DNA shedding, resulting in false-negative findings [17,31,32]. In addition, short-read sequencing cannot reliably determine whether multiple mutations occur in cis or trans configurations, limiting precise structural interpretation [33,34]. Accordingly, integration of high-depth sequencing, phased analysis, or complementary tissue biopsy remains necessary for comprehensive genotyping [24].
Importantly, molecular findings should be interpreted in the context of clinical behavior, radiologic progression patterns, and prior treatment history. Clinically, the detection of compound mutations should prompt a reassessment of therapeutic goals. Rather than pursuing further ALK inhibition indiscriminately, clinicians may consider alternative approaches, including drug rechallenge in selected cases of resensitization, combination therapies, or enrollment in clinical trials targeting non-ALK pathways [30].
Implications of First-Line Lorlatinib
The resistance landscape of ALK-positive NSCLC is changing as lorlatinib is increasingly used in the first-line setting, based on the clinical benefit demonstrated in the phase III CROWN trial [9,35]. Most earlier studies of compound ALK mutations were conducted in patients who had received sequential first- and second-generation ALK TKIs before lorlatinib [17,18,19]. In this context, lorlatinib often selects resistant clones from a tumor population already shaped by prior ALK inhibition [18].
By contrast, resistance after first-line lorlatinib is expected to emerge from an ALK TKI-naïve background, in which pre-existing compound ALK mutations may be less common than after sequential ALK-TKI exposure. Therefore, the spectrum of resistance after first-line lorlatinib may differ from that observed after sequential TKI therapy. Potential mechanisms include de novo on-target ALK mutations, bypass pathway activation, phenotypic adaptation, and histologic transformation [19,36]. This distinction highlights the need for systematic molecular profiling at progression after first-line lorlatinib using tissue biopsy and/or ctDNA [30].
5. Beyond Compound Mutations: Transition to ALK-Independent Resistance
Compound mutations may represent a late ALK-dependent resistance state, but ALK-independent mechanisms can emerge in parallel rather than strictly afterward. Accordingly, resistance evolution should be viewed as branched rather than linear (Figure 1). In some tumors, bypass signaling, lineage plasticity, or epigenetic reprogramming may coexist with compound ALK mutations and progressively reduce ALK dependency.
These ALK-independent resistance mechanisms include activation of bypass signaling pathways, such as MET or HER2, as well as lineage plasticity and epigenetic reprogramming. Among these, MET amplification is one of the most frequently reported bypass mechanisms and has been associated with restoration of downstream MAPK and PI3K–AKT signaling despite continued ALK inhibition [22]. HER2 activation and KRAS mutations have similarly been implicated in sustaining proliferative signaling independently of ALK [24]. In addition, histologic transformation to a small-cell lung cancer phenotype represents an extreme form of lineage plasticity characterized by loss of ALK dependency and resistance to targeted therapy [37]. Recognition of these patterns is clinically important because further escalation of ALK inhibition alone is unlikely to be effective in such contexts. Together, these diverse alterations define the major categories of ALK-independent resistance observed in clinical practice.
Clinically, these transitions may manifest as rapid loss of response to all ALK inhibitors, decreasing ALK mutation allele fractions in plasma despite radiologic progression, or discordant patterns of metastatic spread. Such findings may serve as practical indicators of diminished ALK dependency [19,36]. In such contexts, continued targeting of ALK alone is unlikely to yield durable benefit. Recognizing the transition beyond ALK dependency is therefore critical, as it reframes resistance not as a problem of insufficient inhibition but as a shift in oncogenic reliance. This perspective has important implications for treatment selection and drug development.
6. Future Perspectives
Despite the remarkable evolution of ALK tyrosine kinase inhibitors, no ALK inhibitor beyond lorlatinib has yet received regulatory approval for ALK-positive NSCLC. This underscores the continuing therapeutic challenge posed by resistance after third-generation ALK inhibition. Fourth-generation ALK inhibitors, such as NVL-655/neladalkib, are being developed to retain activity against diverse ALK-mutant oncoproteins, including lorlatinib-resistant compound mutations [29]. However, their clinical role remains investigational, and whether they can broadly overcome the full spectrum of compound ALK mutations remains to be determined.
The emergence of compound ALK mutations suggests that continued escalation of inhibitory potency alone may not be sufficient once the kinase domain has acquired multiple structurally disruptive substitutions. Therefore, future strategies may need to move beyond conventional kinase inhibition. Structure-agnostic approaches are conceptually attractive because they decouple therapeutic activity from precise kinase-domain conformation. Antibody–drug conjugates (ADCs), for example, may exploit tumor-associated surface antigen expression to deliver cytotoxic payloads without requiring direct engagement of the ALK active site [38,39]. Similarly, targeted protein degradation strategies could theoretically eliminate oncogenic ALK protein irrespective of its kinase conformation or mutational status [40].
Combination strategies may also have a role, particularly when ALK-independent mechanisms coexist with on-target resistance. Pairing ALK inhibitors with agents targeting bypass pathways may provide benefit in selected molecular contexts, although such approaches are unlikely to fully overcome resistance driven by highly constrained compound ALK mutations alone. By contrast, immune checkpoint inhibitors have generally shown limited efficacy in ALK-rearranged NSCLC and do not directly address kinase-domain-mediated resistance [41,42].
Future progress will likely depend on integrating therapeutic innovation with dynamic molecular diagnostics. Longitudinal tissue and plasma ctDNA profiling may help distinguish persistent ALK-dependent resistance from emerging ALK-independent escape mechanisms, while predictive structural modeling may support earlier identification of high-risk compound mutation trajectories. However, the evolutionary dynamics underlying compound mutation emergence remain incompletely understood. Current evidence favors clonal selection under prolonged ALK-TKI pressure rather than direct drug-induced mutagenesis. Clarifying these dynamics will require longitudinal genomic analyses with sufficient temporal resolution.
7. Conclusions
The structural classification of single ALK resistance mutations has substantially advanced the clinical management of ALK-rearranged non-small cell lung cancer. However, the emergence of compound ALK mutations represents a distinct and clinically consequential resistance state that cannot be adequately addressed by existing classification schemes [18]. These mutations arise through evolutionary pressure imposed by sequential ALK tyrosine kinase inhibitor therapy and mark a critical inflection point at which ALK dependency reaches its functional limit. Compound mutations not only explain the failure of even third-generation inhibitors such as lorlatinib but also highlight the structural and evolutionary constraints inherent to kinase inhibition-based strategies. Importantly, the occasional observation of paradoxical resensitization underscores that resistance evolution is not strictly unidirectional and that structural interpretation may enable precision therapeutic interventions in selected contexts. At the same time, as lorlatinib moves into the first-line setting, future resistance patterns may differ from those observed after sequential TKI therapy, making systematic molecular profiling at progression increasingly important. Beyond compound mutations, tumors may transition toward ALK-independent survival mechanisms, further limiting the utility of continued ALK-directed inhibition. Together, these observations indicate that future progress in ALK-positive NSCLC will require a conceptual shift from progressively stronger inhibition toward alternative strategies that bypass or exploit kinase domain reprogramming. By integrating structural insight, dynamic molecular monitoring, and structure-agnostic therapeutic approaches, it may be possible to extend disease control beyond the current limits imposed by compound ALK mutations.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
All data analyzed in this study were obtained from previously published sources cited in the reference list.
Conflicts of Interest
The author declares no conflicts of interest.
References
- Soda, M.; Choi, Y.L.; Enomoto, M.; Takada, S.; Yamashita, Y.; Ishikawa, S.; Fujiwara, S.; Watanabe, H.; Kurashina, K.; Hatanaka, H.; et al. Identification of the transforming EML4-ALK fusion gene in non-small-cell lung cancer. Nature 2007, 448, 561–566. [Google Scholar] [CrossRef] [Scilit]
- Koivunen, J.P.; Mermel, C.; Zejnullahu, K.; Murphy, C.; Lifshits, E.; Holmes, A.J.; Choi, H.G.; Kim, J.; Chiang, D.; Thomas, R.; et al. EML4-ALK fusion gene and efficacy of an ALK kinase inhibitor in lung cancer. Clin. Cancer Res. 2008, 14, 4275–4283. [Google Scholar] [CrossRef] [Scilit]
- Kris, M.G.; Johnson, B.E.; Berry, L.D.; Kwiatkowski, D.J.; Iafrate, A.J.; Wistuba, I.I.; Varella-Garcia, M.; Franklin, W.A.; Aronson, S.L.; Su, P.F.; et al. Using multiplexed assays of oncogenic drivers in lung cancers to select targeted drugs. JAMA 2014, 311, 1998–2006. [Google Scholar] [CrossRef] [Scilit]
- Shaw, A.T.; Kim, D.W.; Nakagawa, K.; Seto, T.; Crinó, L.; Ahn, M.J.; De Pas, T.; Besse, B.; Solomon, B.J.; Blackhall, F.; et al. Crizotinib versus chemotherapy in advanced ALK-positive lung cancer. N. Engl. J. Med. 2013, 368, 2385–2394. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Larkins, E.; Blumenthal, G.M.; Chen, H.; He, K.; Agarwal, R.; Gieser, G.; Stephens, O.; Zahalka, E.; Ringgold, K.; Helms, W.; et al. FDA Approval: Alectinib for the Treatment of Metastatic, ALK-Positive Non-Small Cell Lung Cancer Following Crizotinib. Clin. Cancer Res. 2016, 22, 5171–5176. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Soria, J.C.; Tan, D.S.W.; Chiari, R.; Wu, Y.L.; Paz-Ares, L.; Wolf, J.; Geater, S.L.; Orlov, S.; Cortinovis, D.; Yu, C.J.; et al. First-line ceritinib versus platinum-based chemotherapy in advanced ALK-rearranged non-small-cell lung cancer (ASCEND-4): A randomised, open-label, phase 3 study. Lancet 2017, 389, 917–929. [Google Scholar] [CrossRef] [Scilit]
- Camidge, D.R.; Kim, H.R.; Ahn, M.J.; Yang, J.C.H.; Han, J.Y.; Hochmair, M.J.; Lee, K.H.; Delmonte, A.; Garcia Campelo, M.R.; Kim, D.W.; et al. Brigatinib Versus Crizotinib in ALK Inhibitor-Naive Advanced ALK-Positive NSCLC: Final Results of Phase 3 ALTA-1L Trial. J. Thorac. Oncol. 2021, 16, 2091–2108. [Google Scholar] [CrossRef] [Scilit]
- Kazandjian, D.; Blumenthal, G.M.; Chen, H.Y.; He, K.; Patel, M.; Justice, R.; Keegan, P.; Pazdur, R. FDA approval summary: Crizotinib for the treatment of metastatic non-small cell lung cancer with anaplastic lymphoma kinase rearrangements. Oncologist 2014, 19, e5–e11. [Google Scholar] [CrossRef] [Scilit]
- Shaw, A.T.; Bauer, T.M.; de Marinis, F.; Felip, E.; Goto, Y.; Liu, G.; Mazieres, J.; Kim, D.W.; Mok, T.; Polli, A.; et al. First-Line Lorlatinib or Crizotinib in Advanced ALK-Positive Lung Cancer. N. Engl. J. Med. 2020, 383, 2018–2029. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Khozin, S.; Blumenthal, G.M.; Zhang, L.; Tang, S.; Brower, M.; Fox, E.; Helms, W.; Leong, R.; Song, P.; Pan, Y.; et al. FDA approval: Ceritinib for the treatment of metastatic anaplastic lymphoma kinase-positive non-small cell lung cancer. Clin. Cancer Res. 2015, 21, 2436–2439. [Google Scholar] [CrossRef] [Scilit]
- Peters, S.; Camidge, D.R.; Shaw, A.T.; Gadgeel, S.; Ahn, J.S.; Kim, D.W.; Ou, S.I.; Pérol, M.; Dziadziuszko, R.; Rosell, R.; et al. Alectinib versus Crizotinib in Untreated ALK-Positive Non-Small-Cell Lung Cancer. N. Engl. J. Med. 2017, 377, 829–838. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Horn, L.; Wang, Z.; Wu, G.; Poddubskaya, E.; Mok, T.; Reck, M.; Wakelee, H.; Chiappori, A.A.; Lee, D.H.; Breder, V.; et al. Ensartinib vs Crizotinib for Patients With Anaplastic Lymphoma Kinase-Positive Non-Small Cell Lung Cancer: A Randomized Clinical Trial. JAMA Oncol. 2021, 7, 1617–1625. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Solomon, B.J.; Mok, T.; Kim, D.W.; Wu, Y.L.; Nakagawa, K.; Mekhail, T.; Felip, E.; Cappuzzo, F.; Paolini, J.; Usari, T.; et al. First-line crizotinib versus chemotherapy in ALK-positive lung cancer. N. Engl. J. Med. 2014, 371, 2167–2177. [Google Scholar] [CrossRef] [Scilit]
- Zou, H.Y.; Friboulet, L.; Kodack, D.P.; Engstrom, L.D.; Li, Q.; West, M.; Tang, R.W.; Wang, H.; Tsaparikos, K.; Wang, J.; et al. PF-06463922, an ALK/ROS1 Inhibitor, Overcomes Resistance to First and Second Generation ALK Inhibitors in Preclinical Models. Cancer Cell 2015, 28, 70–81. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Solomon, B.J.; Besse, B.; Bauer, T.M.; Felip, E.; Soo, R.A.; Camidge, D.R.; Chiari, R.; Bearz, A.; Lin, C.C.; Gadgeel, S.M.; et al. Lorlatinib in patients with ALK-positive non-small-cell lung cancer: Results from a global phase 2 study. Lancet Oncol. 2018, 19, 1654–1667. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Johnson, T.W.; Richardson, P.F.; Bailey, S.; Brooun, A.; Burke, B.J.; Collins, M.R.; Cui, J.J.; Deal, J.G.; Deng, Y.L.; Dinh, D.; et al. Discovery of (10R)-7-amino-12-fluoro-2,10,16-trimethyl-15-oxo-10,15,16,17-tetrahydro-2H-8,4-(metheno)pyrazolo[4,3-h][2,5,11]-benzoxadiazacyclotetradecine-3-carbonitrile (PF-06463922), a macrocyclic inhibitor of anaplastic lymphoma kinase (ALK) and c-ros oncogene 1 (ROS1) with preclinical brain exposure and broad-spectrum potency against ALK-resistant mutations. J. Med. Chem. 2014, 57, 4720–4744. [Google Scholar] [CrossRef] [Scilit]
- Dagogo-Jack, I.; Rooney, M.; Lin, J.J.; Nagy, R.J.; Yeap, B.Y.; Hubbeling, H.; Chin, E.; Ackil, J.; Farago, A.F.; Hata, A.N.; et al. Treatment with Next-Generation ALK Inhibitors Fuels Plasma ALK Mutation Diversity. Clin. Cancer Res. 2019, 25, 6662–6670. [Google Scholar] [CrossRef] [Scilit]
- Yoda, S.; Lin, J.J.; Lawrence, M.S.; Burke, B.J.; Friboulet, L.; Langenbucher, A.; Dardaei, L.; Prutisto-Chang, K.; Dagogo-Jack, I.; Timofeevski, S.; et al. Sequential ALK Inhibitors Can Select for Lorlatinib-Resistant Compound ALK Mutations in ALK-Positive Lung Cancer. Cancer Discov. 2018, 8, 714–729. [Google Scholar] [CrossRef] [Scilit]
- Recondo, G.; Mezquita, L.; Facchinetti, F.; Planchard, D.; Gazzah, A.; Bigot, L.; Rizvi, A.Z.; Frias, R.L.; Thiery, J.P.; Scoazec, J.Y.; et al. Diverse Resistance Mechanisms to the Third-Generation ALK Inhibitor Lorlatinib in ALK-Rearranged Lung Cancer. Clin. Cancer Res. 2020, 26, 242–255. [Google Scholar] [CrossRef] [Scilit]
- Choi, Y.L.; Soda, M.; Yamashita, Y.; Ueno, T.; Takashima, J.; Nakajima, T.; Yatabe, Y.; Takeuchi, K.; Hamada, T.; Haruta, H.; et al. EML4-ALK mutations in lung cancer that confer resistance to ALK inhibitors. N. Engl. J. Med. 2010, 363, 1734–1739. [Google Scholar] [CrossRef] [Scilit]
- Katayama, R.; Shaw, A.T.; Khan, T.M.; Mino-Kenudson, M.; Solomon, B.J.; Halmos, B.; Jessop, N.A.; Wain, J.C.; Yeo, A.T.; Benes, C.; et al. Mechanisms of acquired crizotinib resistance in ALK-rearranged lung Cancers. Sci. Transl. Med. 2012, 4, 120ra17. [Google Scholar] [CrossRef] [Scilit]
- Doebele, R.C.; Pilling, A.B.; Aisner, D.L.; Kutateladze, T.G.; Le, A.T.; Weickhardt, A.J.; Kondo, K.L.; Linderman, D.J.; Heasley, L.E.; Franklin, W.A.; et al. Mechanisms of resistance to crizotinib in patients with ALK gene rearranged non-small cell lung cancer. Clin. Cancer Res. 2012, 18, 1472–1482. [Google Scholar] [CrossRef] [Scilit]
- Hatcher, J.M.; Bahcall, M.; Choi, H.G.; Gao, Y.; Sim, T.; George, R.; Jänne, P.A.; Gray, N.S. Discovery of Inhibitors That Overcome the G1202R Anaplastic Lymphoma Kinase Resistance Mutation. J. Med. Chem. 2015, 58, 9296–9308. [Google Scholar] [CrossRef] [Scilit]
- Gainor, J.F.; Dardaei, L.; Yoda, S.; Friboulet, L.; Leshchiner, I.; Katayama, R.; Dagogo-Jack, I.; Gadgeel, S.; Schultz, K.; Singh, M.; et al. Molecular Mechanisms of Resistance to First- and Second-Generation ALK Inhibitors in ALK-Rearranged Lung Cancer. Cancer Discov. 2016, 6, 1118–1133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toyokawa, G.; Hirai, F.; Inamasu, E.; Yoshida, T.; Nosaki, K.; Takenaka, T.; Yamaguchi, M.; Seto, T.; Takenoyama, M.; Ichinose, Y. Secondary mutations at I1171 in the ALK gene confer resistance to both Crizotinib and Alectinib. J. Thorac. Oncol. 2014, 9, e86–e87. [Google Scholar] [CrossRef] [Scilit]
- Katayama, R.; Friboulet, L.; Koike, S.; Lockerman, E.L.; Khan, T.M.; Gainor, J.F.; Iafrate, A.J.; Takeuchi, K.; Taiji, M.; Okuno, Y.; et al. Two novel ALK mutations mediate acquired resistance to the next-generation ALK inhibitor alectinib. Clin. Cancer Res. 2014, 20, 5686–5696. [Google Scholar] [CrossRef] [Scilit]
- Heuckmann, J.M.; Balke-Want, H.; Malchers, F.; Peifer, M.; Sos, M.L.; Koker, M.; Meder, L.; Lovly, C.M.; Heukamp, L.C.; Pao, W.; et al. Differential protein stability and ALK inhibitor sensitivity of EML4-ALK fusion variants. Clin. Cancer Res. 2012, 18, 4682–4690. [Google Scholar] [CrossRef] [Scilit]
- Sakaguchi, H.; Katayama, R.; Matsumoto, M.; Nishiyama, A.; Matsumoto, K.; Tajima, A.; Miyagi, S.; Toyama, T.; Mizuta, H.; Furugaki, K.; et al. Plasma cfDNA analysis of alectinib resistance-related gene alterations in the J-ALEX study. ESMO Open 2025, 10, 105574. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lin, J.J.; Horan, J.C.; Tangpeerachaikul, A.; Swalduz, A.; Valdivia, A.; Johnson, M.L.; Besse, B.; Camidge, D.R.; Fujino, T.; Yoda, S.; et al. NVL-655 Is a Selective and Brain-Penetrant Inhibitor of Diverse ALK-Mutant Oncoproteins, Including Lorlatinib-Resistant Compound Mutations. Cancer Discov. 2024, 14, 2367–2386. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaw, A.T.; Friboulet, L.; Leshchiner, I.; Gainor, J.F.; Bergqvist, S.; Brooun, A.; Burke, B.J.; Deng, Y.L.; Liu, W.; Dardaei, L.; et al. Resensitization to Crizotinib by the Lorlatinib ALK Resistance Mutation L1198F. N. Engl. J. Med. 2016, 374, 54–61. [Google Scholar] [CrossRef] [Scilit]
- Aldea, M.; Hendriks, L.; Mezquita, L.; Jovelet, C.; Planchard, D.; Auclin, E.; Remon, J.; Howarth, K.; Benitez, J.C.; Gazzah, A.; et al. Circulating Tumor DNA Analysis for Patients with Oncogene-Addicted NSCLC With Isolated Central Nervous System Progression. J. Thorac. Oncol. 2020, 15, 383–391. [Google Scholar] [CrossRef] [Scilit]
- De Mattos-Arruda, L.; Mayor, R.; Ng, C.K.Y.; Weigelt, B.; Martínez-Ricarte, F.; Torrejon, D.; Oliveira, M.; Arias, A.; Raventos, C.; Tang, J.; et al. Cerebrospinal fluid-derived circulating tumour DNA better represents the genomic alterations of brain tumours than plasma. Nat. Commun. 2015, 6, 8839. [Google Scholar] [CrossRef] [Scilit]
- Rolfo, C.; Mack, P.; Scagliotti, G.V.; Aggarwal, C.; Arcila, M.E.; Barlesi, F.; Bivona, T.; Diehn, M.; Dive, C.; Dziadziuszko, R.; et al. Liquid Biopsy for Advanced NSCLC: A Consensus Statement From the International Association for the Study of Lung Cancer. J. Thorac. Oncol. 2021, 16, 1647–1662. [Google Scholar] [CrossRef] [Scilit]
- Goodwin, S.; McPherson, J.D.; McCombie, W.R. Coming of age: Ten years of next-generation sequencing technologies. Nat. Rev. Genet. 2016, 17, 333–351. [Google Scholar] [CrossRef] [Scilit]
- Solomon, B.J.; Liu, G.; Felip, E.; Mok, T.S.K.; Soo, R.A.; Mazieres, J.; Shaw, A.T.; de Marinis, F.; Goto, Y.; Wu, Y.L.; et al. Lorlatinib Versus Crizotinib in Patients With Advanced ALK-Positive Non-Small Cell Lung Cancer: 5-Year Outcomes from the Phase III CROWN Study. J. Clin. Oncol. 2024, 42, 3400–3409. [Google Scholar] [CrossRef] [Scilit]
- Meador, C.B.; Piotrowska, Z. Biology and impact of lineage plasticity in ALK-positive NSCLC: A narrative review. Transl. Lung Cancer Res. 2023, 12, 837–856. [Google Scholar] [CrossRef] [Scilit]
- Fujita, S.; Masago, K.; Katakami, N.; Yatabe, Y. Transformation to SCLC after Treatment with the ALK Inhibitor Alectinib. J. Thorac. Oncol. 2016, 11, e67–e72. [Google Scholar] [CrossRef] [Scilit]
- Xie, H.; Adjei, A.A. Antibody-Drug Conjugates for the Therapy of Thoracic Malignancies. J. Thorac. Oncol. 2019, 14, 358–376. [Google Scholar] [CrossRef] [Scilit]
- Pacheco, J.M.; Camidge, D.R. Antibody drug conjugates in thoracic malignancies. Lung Cancer 2018, 124, 260–269. [Google Scholar] [CrossRef] [Scilit]
- Burslem, G.M.; Crews, C.M. Proteolysis-Targeting Chimeras as Therapeutics and Tools for Biological Discovery. Cell 2020, 181, 102–114. [Google Scholar] [CrossRef] [Scilit]
- Gainor, J.F.; Shaw, A.T.; Sequist, L.V.; Fu, X.; Azzoli, C.G.; Piotrowska, Z.; Huynh, T.G.; Zhao, L.; Fulton, L.; Schultz, K.R.; et al. EGFR Mutations and ALK Rearrangements Are Associated with Low Response Rates to PD-1 Pathway Blockade in Non-Small Cell Lung Cancer: A Retrospective Analysis. Clin. Cancer Res. 2016, 22, 4585–4593. [Google Scholar] [CrossRef] [Scilit]
- Rizvi, H.; Sanchez-Vega, F.; La, K.; Chatila, W.; Jonsson, P.; Halpenny, D.; Plodkowski, A.; Long, N.; Sauter, J.L.; Rekhtman, N.; et al. Molecular Determinants of Response to Anti-Programmed Cell Death (PD)-1 and Anti-Programmed Death-Ligand 1 (PD-L1) Blockade in Patients with Non-Small-Cell Lung Cancer Profiled with Targeted Next-Generation Sequencing. J. Clin. Oncol. 2018, 36, 1645, Erratum in J. Clin. Oncol. 2018, 36, 633–641. https://doi.org/10.1200/jco.2017.75.3384. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the author. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.