Systematic Review

Gamification in Diabetes Blood Glucose Management: A Systematic Review of Systematic Reviews

1
School of Public Health, Texas A&M University, College Station, TX 77843, USA
2
College of Nursing, Texas A&M University, Bryan, TX 77807, USA
3
Medical Sciences Library, Texas A&M University, College Station, TX 77843, USA
*
Author to whom correspondence should be addressed.
Diabetology 2026, 7(6), 111; https://doi.org/10.3390/diabetology7060111
Submission received: 18 February 2026 / Revised: 16 May 2026 / Accepted: 3 June 2026 / Published: 10 June 2026

Abstract

Background: Diabetes is the eighth-leading cause of death in the U.S. and poor blood glucose (BG) management is associated with serious long-term complications. While educational interventions have been shown to improve health outcomes among individuals with diabetes, evidence regarding the effectiveness of gamification remains inconsistent. The purpose of this study is to evaluate existing systematic reviews on the effectiveness of gamification interventions for blood glucose management among individuals with diabetes. Method: A systematic literature search was conducted using electronic databases including Medline, Embase, Cochrane library, APA PsycInfo, Web of Science, and Campbell systematic reviews. Studies published in English with gamification as the primary intervention and BG or HbA1c as primary outcomes were included in the review. Studies were excluded if they involved gestational diabetes, used gamification alongside other interventions, or were classified as gray literature. The quality of each review was assessed using a modified AMSTAR 2 tool. Results: Of 382 articles screened, eight systematic reviews were included in the final review. In the quality assessment, four reviews fulfilled 11 out of 13 (84.6%) of the critical appraisal items. All (100%) of the reviews demonstrated reduction in HbA1c; however, the reduction was statistically significant in only one review. Conclusions: Gamification shows potential in assisting with glycemic control, with reviews finding a decrease in HbA1c among patients with diabetes. More rigorous, large-scale studies need to be done to understand gamification as a method of diabetes management and long-term outcomes.

1. Introduction

In the United States, diabetes is one of the most prevalent chronic health conditions, affecting an estimated 11.6% (38.4 million) of the population, and is currently the seventh-leading cause of death [1,2]. Diabetes represents a major public health challenge because of its long-term consequences on an individual’s well-being and the impact it has on healthcare systems. Poor diabetes management can lead to a variety of serious and often irreversible complications, such as cardiovascular disease, retinopathy, neuropathy, and nephropathy [3]. These diabetes-related complications not only decrease patients’ quality of life but can also result in a heavy financial and emotional burden for individuals, families, and the communities affected by them [4].
Managing diabetes involves routine blood glucose monitoring, medication adherence, maintaining a healthy diet, and engaging in regular physical activity. While these behaviors are essential, sustaining them over time can be difficult, particularly when motivation or support is lacking [5]. To address these challenges, diabetes self-management education (DSME) programs have become an integral component of diabetes care. These programs aim to help patients understand their condition, build self-efficacy, and develop sustainable management habits [6]. Research has shown that DSME programs can improve patient knowledge and lead to better clinical outcomes [7]. However, keeping patients engaged in these programs long term remains one of the biggest barriers to success. In recent years, researchers and clinicians have increasingly explored innovative approaches to enhance patient engagement and motivation. One of the most promising emerging strategies is gamification, which involves the use of game-like elements, such as points, badges, levels, leaderboards, and rewards in non-game settings including healthcare [8]. When applied to healthcare, gamification aims to make behavior more enjoyable, interactive, and sustainable. In diabetes care, gamified interventions have been used to encourage consistent blood glucose monitoring, medication adherence, and healthy lifestyle choices [9]. Early evidence suggests that these interventions can increase engagement and, in some cases, improve self-management outcomes [10].
However, the overall evidence regarding the effectiveness of gamification remains mixed. While some studies have reported meaningful improvements in blood glucose management and self-management behaviors [11], others have found only insignificant or short-term effects [12]. Several systematic reviews have tried to summarize findings from individual studies, but their conclusions often vary due to the differences in scope, study quality, and methodology [13]. So far, no comprehensive synthesis has combined these systematic reviews to create a broader understanding of gamification’s overall impact on diabetes management.
Thus, this systematic review of systematic reviews aims to evaluate the existing evidence on gamification-based interventions for diabetes self-management. Specifically, it seeks to determine how gamification affects blood glucose management and patient engagement in self-care behaviors. By integrating findings across multiple reviews, this study will provide a clearer, evidence-based understanding of whether gamification enhances diabetes outcomes, as well as highlight directions for future intervention design and evaluation.

2. Methods

2.1. Study Selection

The criteria for inclusions were as follows: (1) were original research studies (systematic review with or without meta-analysis), (2) studied people with type 1 or type 2 diabetes, (3) used a method of gamification as the primary intervention and (4) used blood glucose or HbA1c as the major clinical outcome of the study. Similarly, research studies were excluded if (1) they were not reported in English, (2) they did not include gamification as an intervention or were mixed with other types of intervention, (3) they included participants with gestational diabetes, or (4) they belonged to gray literature. The reporting of this systematic review was guided by the standards of the Preferred Reporting Items for Systematic Review and Meta-Analysis (PRISMA) statement 2020 [14]. A protocol for this review was registered on the Open Science Framework (OSF) on 23 July 2025 (https://doi.org/10.17605/OSF.IO/K9XUS).

2.2. Database Search

A comprehensive search strategy was developed by a medical sciences librarian who is experienced in systematic review searching. The search was piloted against seed articles that were selected by the review team, and a consensus was made regarding search terms and inclusion criteria for the final search. This search consisted of two concepts (diabetes and gamification), and a third concept to narrow down to review and meta-analysis papers was added. There were no date restrictions placed on the search, and only sources of evidence that were fully available in the English language were considered for inclusion. If full texts were not available, authors were contacted, and articles were excluded if authors did not respond or were unwilling to provide the full manuscript.
On 17 June 2025, electronic databases Medline (OVID), Embase (OVID), Cochrane Library, APA PsycInfo (EBSCO), and Web of Science were searched. Additionally, a manual search of the journal Campbell Collaboration Systematic Reviews was conducted the same day. Upon completion of the full text screening phase, both forward and backward citation searching was conducted on 28 July 2025 by the medical sciences librarian using citation chaser [15]. Detailed description of searching is described in Supplementary Materials File S1.

2.3. Screening and Data Extraction

Results from the database searches and journal search were uploaded into Covidence, a web-based collaboration platform that streamlines the production of systematic and other literature reviews for screening [16]. Citations were deduplicated automatically as they were imported into Covidence, and any remaining duplicates were removed manually. Three independent reviewers screened the titles and abstracts of all identified records for eligibility. Full texts of potentially relevant sources were then retrieved and assessed against the inclusion criteria independently by at least two reviewers. Articles excluded at this stage were documented along with the reasons for exclusion. Any disagreements between reviewers were resolved through discussion. Data extraction of the final articles was done independently by the two reviewers. Findings were summarized using both narrative synthesis and structured tables. Table 1 presents the characteristics of the included reviews, Table 2 summarizes the risk of bias assessments and Table 3 provides an overview of the reported outcomes.

2.4. Quality Assessment

The quality assessment of each systematic review was done by utilizing the AMSTAR2 protocol. AMSTAR 2 is a critical appraisal tool designed to evaluate the methodological quality of systematic reviews that include randomized or non-randomized studies. It consists of 16 items, of which 7 are considered critical domains (items 2, 4, 7, 9, 11, 13, and 15) that have a substantial impact on the overall confidence rating of a review [26]. As our study focused on a systematic review of systematic reviews, items #11, 12, and 15 in the AMSTAR2 were deemed not applicable as they focused on meta-analysis. Therefore, we had a total of 13 items, out of which items # 2, 4, 7, 9, and 13 served as critical items. Items # 2, 4, 7, 9, and 13 were related to “registration of protocol”, “comprehensive literature search”, “list of excluded studies and justification for the exclusion”, “use of satisfactory techniques to assess the risk of bias of individual systematic review”, and “accounting for risk of bias in primary studies when interpreting or discussing the results”, respectively. Because we modified the AMSTAR 2 assessment approach, instead of categorizing the quality of each review as high, moderate, low, or critically low as described by Shea et al., we calculated the number of evaluation items met among the 13 assessed items and presented this as a percentage, with higher percentages indicating higher methodological quality of the systematic review [26]. Quality assessment was done independently by two reviewers, and any disagreement was resolved through discussion.

2.5. Corrected Covered Area (CCA) Calculation

In the systematic review of systematic reviews with or without meta-analysis, it might be challenging to examine all available evidence from the primary studies, as many of the primary studies are usually included in more than one systematic review. The pooled result would then give disproportionate statistical power to multiple primary studies [27]. An analysis obtained by summing up the results of the reviews could introduce major overlap and might result in many primary studies being included more than once, resulting in biased results [28]. To address this issue, Pieper et al. [29] introduced the concept of corrected covered area (CCA). In this study, CCA was calculated by utilizing the statistical tool developed by Pieper et al. [29]. Detailed description of CCA calculation is provided in Supplementary Materials File S2.

3. Result

3.1. Result of Study Search

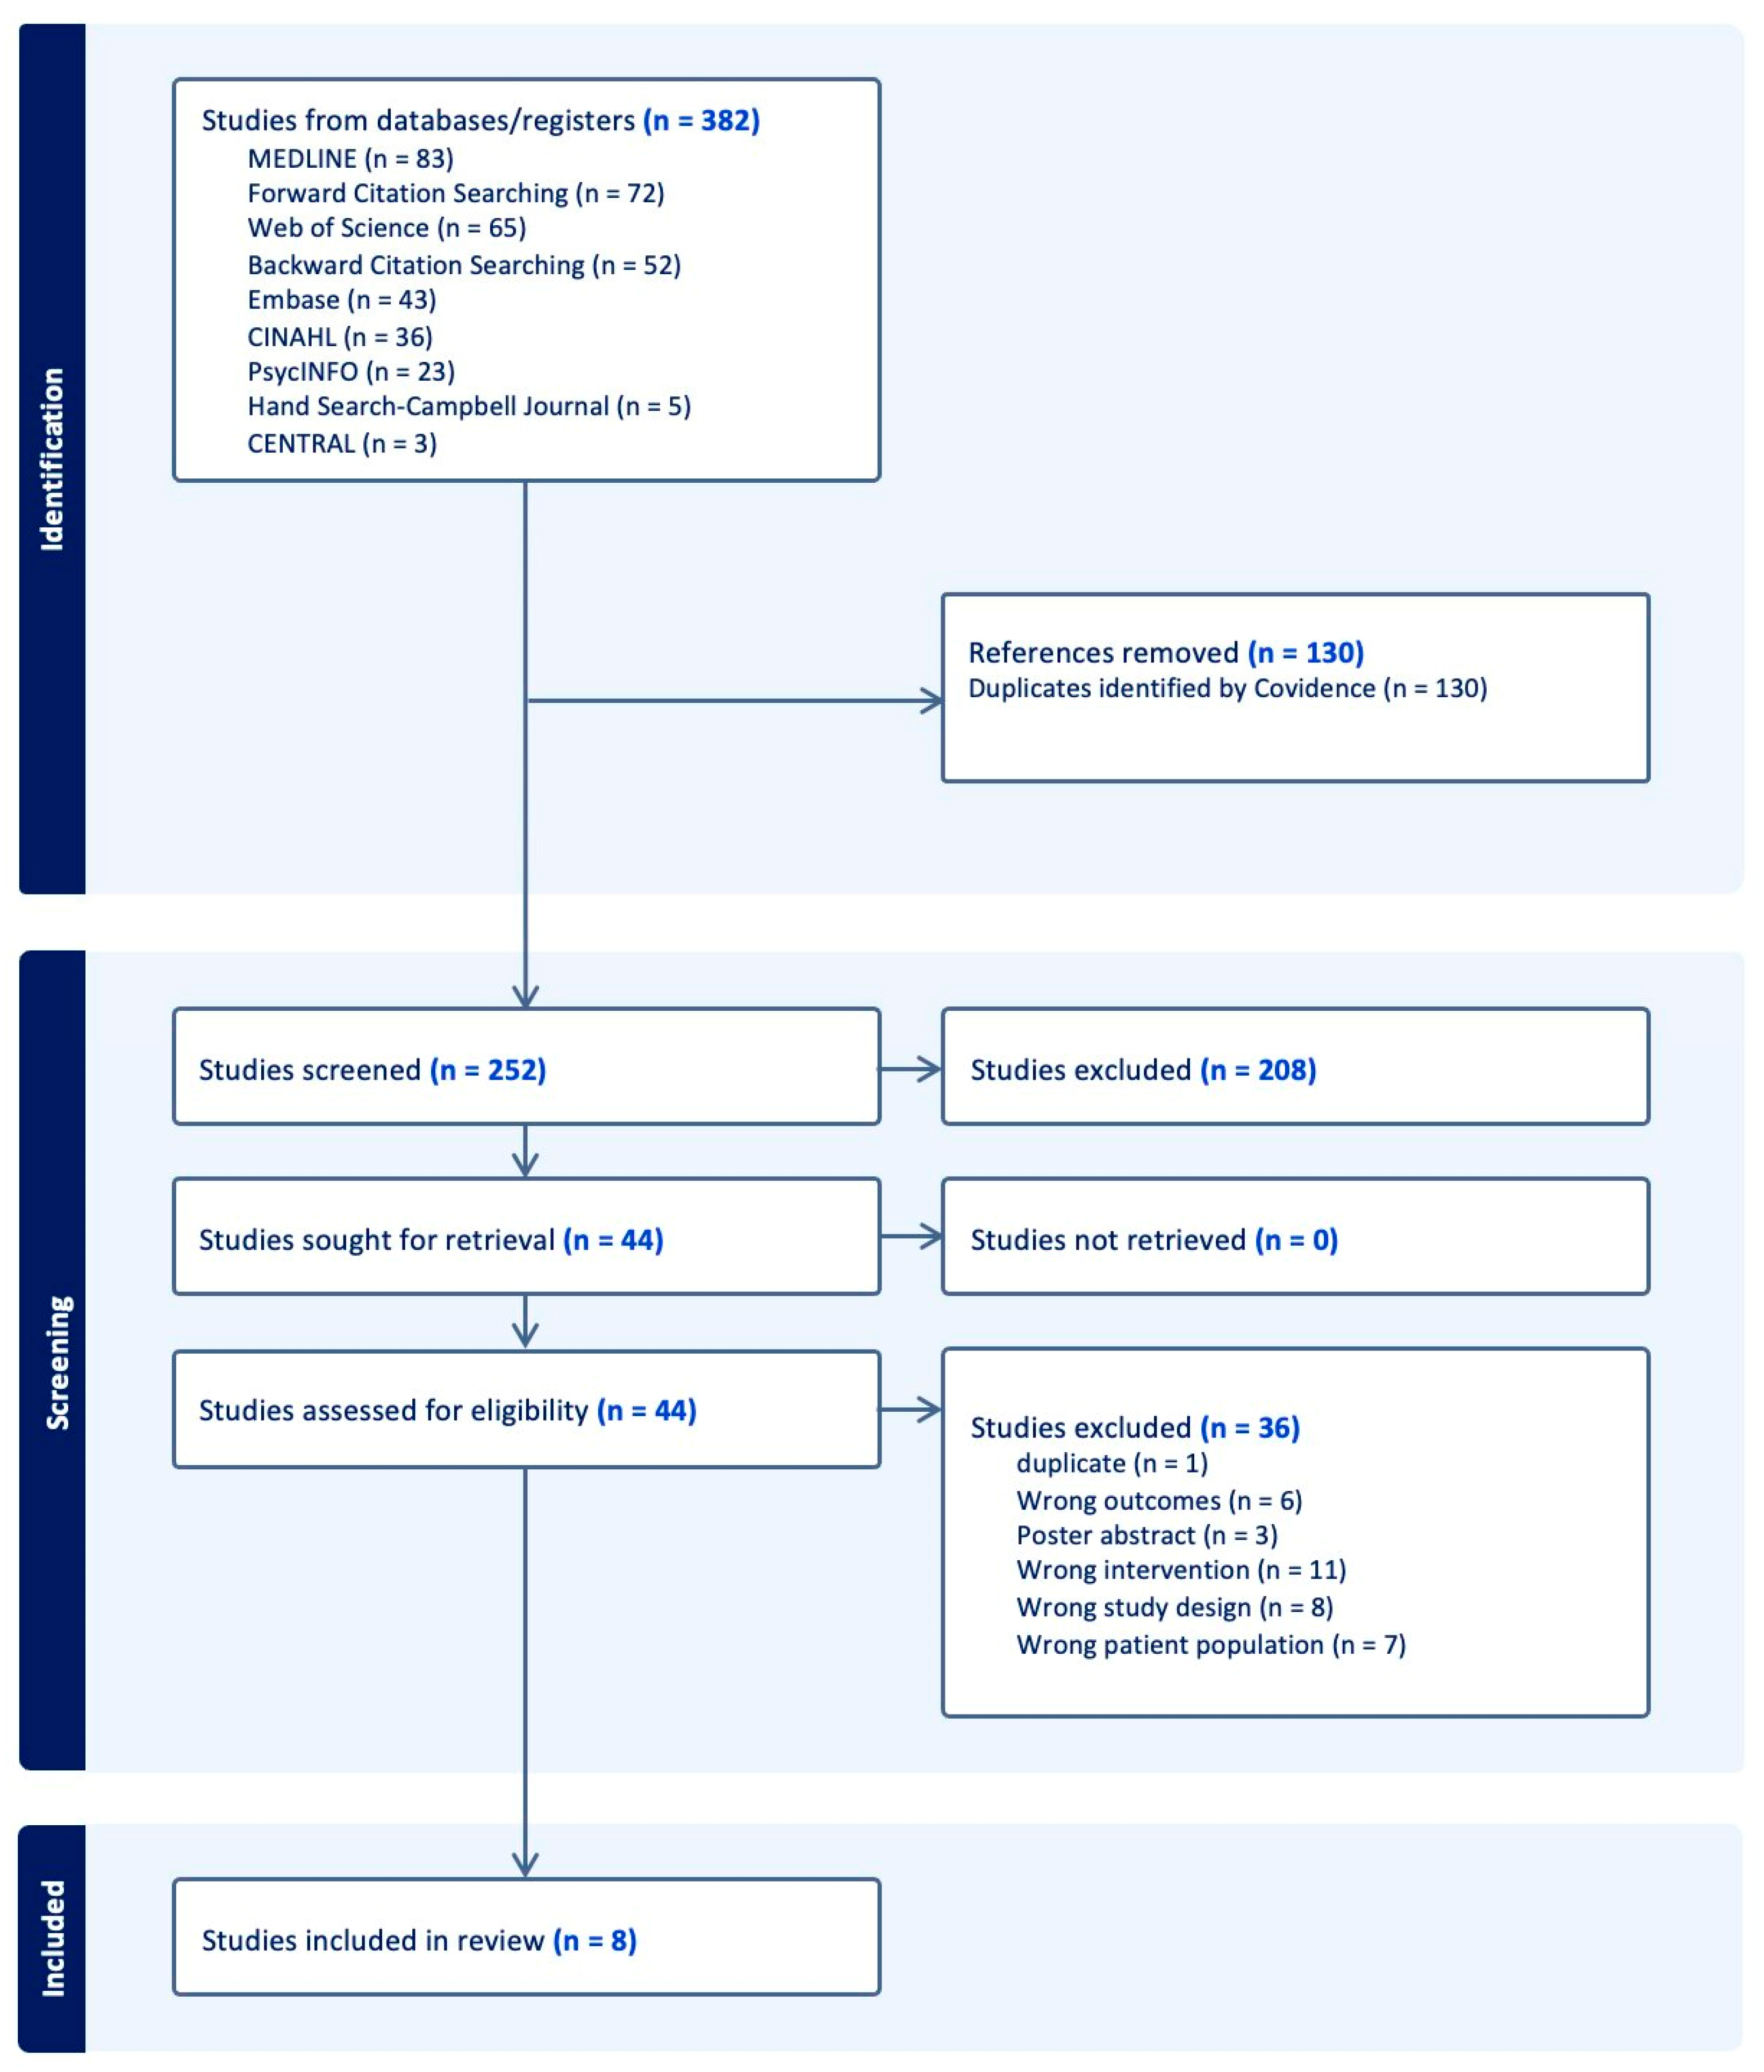
The electronic databases, manual journal search, and forward and backward citation search yielded a total of 382 studies imported for screening. After duplicates were removed (n = 130), titles and abstracts were assessed for eligibility (n = 252). Irrelevant citations were removed (n = 208). Full texts were evaluated against the eligibility criteria (n = 44), and 36 studies were excluded with reasons. The final review consisted of eight studies (Figure 1).

3.2. Descriptive Statistics of Included Review

All of the eight included systematic reviews were published between 2015 and 2024. The total number of individual studies within these systematic reviews was 69, and they were predominantly (87%) randomized controlled trials (RCTs). The remainder of the studies (13%) were quasi-experimental and observational studies. In terms of location, one study was conducted across both the United States and Qatar. Out of the remaining 68 studies, 31 (45.58%) were conducted in North America, 24 (35.29%) in Europe, 11 (16.17%) in Asia, and 2 (2.94%) in Australia. The modalities of gamification intervention in these studies ranged from video games, smartphone games, digital handheld games, gamified behavior or education systems, exergames, and serious educational games. A detailed description of individual interventions in each systematic review is provided in Table 1.

3.3. Result of Quality Assessment

The revised AMSTAR2 was utilized to assess the quality of each systematic review. Regarding the critical domain items, four (50%) systematic reviews failed to meet item #2, which was related to protocol registration, and two (25%) systematic reviews did not address item #13, which was related to consideration of risk of bias when interpreting or discussing the results. Among non-critical domains, all eight (100%) reviews failed to report the sources of funding for the individual studies included in each systematic review. Overall, out of eight reviews, one (12.5%) review fulfilled 8 of 13 (61.5%) appraisal items, two studies fulfilled 10 of 13 (76.9%) items, four studies fulfilled 11 of 13 (84.6%) items, and one study fulfilled 12 of 13 (92.3%) items. A detailed description of the quality assessment of all eight systematic reviews is included in Table 2.

3.4. Result of CCA Calculation

Detailed description on calculation of CCA is provided in Supplementary Materials File S2. The calculated CCA in this study was 16.23%, implying a very high overlap of primary studies.

3.5. Effect of Gamification on Blood Glucose and HbA1c Level

The effectiveness of gamification in blood glucose and HbA1c level management is summarized in Table 3. In a meta-analysis by Yao et al., gamification interventions were associated with a modest reduction in HbA1c levels (mean difference [MD] = −0.09%, 95% CI: −0.29, 0.10, p = 0.36); however, this improvement was not statistically significant [17]. Six among 10 studies in Ossenbrink et al. analyzed HbA1c levels, among which two studies revealed significant reduction [18]. Kerfoot et al. and Kempf and Martin showed significant reduction in HbA1c levels between intervention and control group at 48 weeks (p = 0.048) and 12 weeks (p < 0.001) post intervention, respectively [24,25]. Around 67% (six out of nine) of studies in Brady et al. analyzed HbA1c as the outcome measure [19]. Five of these studies had a reduction in HbA1c levels; however, only two studies, Kerfoot et al. and Kempf and Martin, had a significant reduction [24,25].
In another meta-analysis with a total of 1045 sample size, Lim et al. reported a minimal effect size of game-based exercise intervention (d = −0.16, 95% CI = −0.45, 0.14, p = 0.29), although this effect was not statistically significant [20]. Similar findings of minimal but non-significant reductions in HbA1c levels among intervention groups were reported in reviews by Shiau et al. (Hedges’s g = −0.06, p = 0.54), Cabrera et al. (MD = −0.12, 95% CI = −0.57, 0.33), and Christensen (2016) (MD = −0.10, 95% CI = −0.33, 0.14) [11,22,23]. In contrast, Kaihara et al. observed a significant decrease in HbA1c following gamification interventions (MD = −0.21, 95% CI = −0.37, −0.05) [21].

3.6. Effect of Gamification on Change in Confidence and Knowledge Regarding Diabetes Management

Studies assessing change in confidence and knowledge level following gamification intervention were limited. A meta-analysis to assess diabetes self-efficacy (Hedges’s g = 0.22, p = 0.32) and diabetes knowledge (mean difference = 0.17, p = 0.46) following gamification intervention found no significant difference between the intervention and control group [11]. (Table 3).

4. Discussion

Six of the reviewed studies conducted a meta-analysis, all of which demonstrated minor to moderate reduction in HbA1c levels [11,17,20,21,22,23]. Except for the meta-analysis by Kaihara et al., these reductions were not statistically significant [21]. The two systematic reviews without meta-analysis by Ossenbrink et al. and Brady et al. also reported a decrease in HbA1c; however, these findings were not statistically significant in the majority of included studies [18,19]. A notable issue demonstrated in this review is the substantial overlap of primary studies across included systematic reviews as demonstrated by the calculated CCA of 16.23 percentage. Several primary studies, particularly those conducted by Kerfoot et al. [24] and Kempf and Martin [25], were repeatedly included across multiple reviews, suggesting that the evidence base is derived from a relatively small and recurring set of primary studies. This overlap suggests that the apparent consistency in HbA1c outcomes might be due to repeated synthesis of the same underlying studies. This is particularly relevant to the meta-analysis by Kaihara et al. which was the only review demonstrating a statistically significant reduction in HbA1c [21]. This finding appears to be largely driven by the same recurring studies of Kerfoot et al. and Kempf and Martin [24,25]. Therefore, the observed significance in this study may reflect the influence of a small number of positive studies rather than a broadly supported effect across diverse interventions and population. In contrast other studies like Yao et al. included a broader and more heterogenous set of studies, many of which reported minimal or non-significant effects, which likely attenuated the overall pooled effect [17]. This implies that difference in study selection and relative influence of a small number of positive trials might partly explain the divergent conclusions across meta-analysis. A commonly identified limitation across reviews was the lack of homogeneity in gamification modalities, which ranged from video games and gamified education system to exergames and serious games [11,17,18,19,20,23]. Small sample sizes in the included studies were another frequently cited concern [11,17,20]. Cabrera et al. and Brady et al. additionally noted limited diversity among study populations, with most research conducted in North America and Europe [19,22]. The absence of information on potential confounders like body weight, diabetic medication, and disease duration may also have contributed to variability in study outcomes [19,21].
The concept of gamification is relatively new and started appearing in mainstream vocabulary around 2010. Gamification has been applied in various domains including education, marketing, human resources, training, and healthcare [30]. Commonly employed elements of gamification include marketplace and economics, digital rewards, real world prizes, avatars, agents, competition, teams, feedback, 3-D environment, ranks and levels, and time pressure [31,32]. The use and effectiveness of gamification in healthcare is relatively new and continuously emerging. In a systematic review performed by Johnson et al., gamification in health and wellness demonstrated positive effects in 59% of the studies, whereas in 41% of studies, a mixed effect was noted [8]. The evidence was strongest for behavioral outcomes, particularly physical activity. With respect to diabetes care, the utilization of gamification is relatively new and is continuously emerging as evidenced by a study by Priesterroth et al., where only 1.4 out of 17 gamification techniques were implemented in freely available diabetes self-management applications in the Google Play store [33]. Current evidence on the effect of gamification on blood glucose management is heterogenous with some studies demonstrating benefit while others show no significant benefit [12,24,25]. Although the direction of benefit of gamification in our review is consistent, the certainty is low due to lack of statistical significance. Also, it is important to note that all the reviews in our study have used different gamification approaches, and therefore it is difficult to compare the effect of similar gamification methods.
Quality assessment revealed that among the eight systematic reviews included in this review, only four of them (50%) met at least 80% of the quality assessment criteria. One of the striking revelations was that half of the reviews failed to fulfil the critical domain related to protocol registration. Protocol registration prior to commencement of the review serves important benefits. It helps in reducing the review authors’ biases, promotes transparency of methods and minimizes duplication. Similarly, it also provides an opportunity for the team to plan the logistics and resources to conduct the review [34]. A positive association of protocol registration with review quality is also well documented. In a study by Sideri et al., an average increase of 6.6% in quality assessment was found when a comparison was made between registered and unregistered systematic reviews [35]. Despite these benefits, the protocol registration in published systematic reviews or meta-analyses is substantially low as evidenced by a cross-sectional analysis done by Tawfik et al. [36]. This study showed that 44.2% of the authors failed to register the protocol prior to the submission of their systematic review or meta-analysis during the period 2010 to 2016. Most common (45%) cited reasons by the authors were lack of protocol registration as a mandatory prerequisite for the publication and lack of awareness on the importance of protocol registration [36].
Among non-critical domains, all the reviews failed to provide information on the source of funding for primary studies included in the review. The evidence of industry sponsored trials favoring a better outcome is well documented. In a systematic review performed by Lundh et al., compared to non-industry sponsored studies, those with industry sponsored studies had favorable efficacy results (RR = 1.27, 95% CI = 1.17, 1.37) and more favorable conclusions (RR = 1.34, 95% CI = 1.19, 1.51) [37]. Despite this evidence, the proportion of systematic reviews mentioning funding sources of the primary studies is minimal, as evidenced by a review performed by Faggion Jr et al., where only 45 (31%) out of 146 systematic reviews reported the funding sources of primary studies [38]. In recent years, recognition of sponsorship bias has raised concerns about the reliability of evidence underlying many commonly used therapeutics and preventive interventions. Sponsorship bias is the process of favoring the sponsor’s aim through distortion of design and reporting of studies [39]. In meta-research assessing industry sponsorship bias in 28 randomized controlled trials (RCTs) of digital cognitive behavioral therapy for insomnia, a significant association was noted between risk of sponsorship bias and lower levels of methodological quality [X2 (1) = 4.861; p = 0.027] [40]. In the context of digital health and gamifications, this concern is relevant, as many platforms are developed or supported by commercial entities and the absence of a funding source in all of the primary studies of systematic reviews limits our ability to assess the influence of sponsors on study outcomes. A considerable effort therefore needs to be made to increase the reporting of funding sources of primary studies in systematic reviews primarily involving gamification.
There are some limitations that need to be considered. There were overlaps of primary studies across the included systematic reviews, where several of same trials were included in different analyses as evidenced by the calculated CCA of 16.23 percent. In our study, this overlap might have introduced redundancy in the evidence and influenced the perceived consistency of results. The observed overlap among systematic reviews underscores the importance of careful interpretation of pooled conclusions, as repeated inclusions of the same primary studies may overrepresent certain findings. Furthermore, as this review is based on published systematic reviews rather than individual primary studies, examination of how differences in study design, population characteristics, or interventions may have affected the outcome could not be conducted in detail. Similarly, all the primary studies of the systematic reviews lacked funding transparency, thereby reducing our confidence in the observed clinical effects, including outcomes such as HbA1c, and highlights the need for more rigorous and transparent reporting in future studies. The concept of a systematic review of systematic reviews is emerging, and there are limited tools to perform the quality assessment of these reviews. As we precluded the domains involving meta-analysis from the AMSTAR2 tool, the quality assessment done in our review needs to be interpreted with caution. Similarly, given the wide variation in gamification techniques implemented in the review, comparing the effectiveness of similar gamification modalities was difficult. Furthermore, with the majority of studies concentrated in developed countries, generalization of these results to resource-limited settings where access to high-speed internet and gamification modalities are limited, may be constrained.

5. Conclusions

Gamification interventions appear to have a potentially positive effect on improving glucose levels and diabetes management. However, the majority of studies did not demonstrate statistically significant reductions in glycemia outcomes, resulting in a low level of certainty regarding the magnitude and consistency of these effects. The observed heterogeneity of gamification techniques, along with limited sample size, and variation in study designs and outcome measures, likely contributed to the mixed findings across studies. Future studies should focus on adopting a more unified theoretical framework to define, implement, and evaluate gamification components, which might allow for robust comparisons across interventions and strengthen the evidence base for their effectiveness. Additionally, future research should emphasize a clear description of the specific gaming elements used, such as rewards and feedback, so that it makes it easier to understand the component driving the observed benefits. Furthermore, studies with longer follow-up periods are needed to evaluate whether the observed benefits can be sustained over time. Finally, it is imperative that future studies improve transparency on funding sources to strengthen confidence in the findings within this rapidly evolving field.

Supplementary Materials

The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/diabetology7060111/s1, File S1: Database Searches; File S2: Corrected Covered Area (CCA) calculation.

Author Contributions

Conceptualization, Y.-C.H.; methodology, Y.-C.H., D.L., S.S. and M.L.; validation, Y.-C.H., S.S. and M.L.; formal analysis, S.S. and M.L.; data curation, D.L.; writing—original draft preparation, Y.-C.H., D.L., S.S. and M.L.; writing—review and editing, Y.-C.H., D.L., S.S. and M.L.; supervision, Y.-C.H. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

Not applicable.

Informed Consent Statement

Not applicable.

Data Availability Statement

No new data were created or analyzed in this study.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. Centers for Disease Control and Prevention (CDC). National Diabetes Statistics Report: Data & Research. Available online: https://www.cdc.gov/diabetes/php/data-research/index.html (accessed on 5 October 2025).
  2. Centers for Disease Control and Prevention (CDC). FastStats—Leading Causes of Death. Available online: https://www.cdc.gov/nchs/fastats/leading-causes-of-death.htm (accessed on 6 October 2025).
  3. American Diabetes Association Professional Practice Committee for Diabetes. Introduction and Methodology: Standards of Care in Diabetes—2026. Diabetes Care 2026, 49, S1–S5. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Butt, M.D.; Ong, S.C.; Rafiq, A.; Kalam, M.N.; Sajjad, A.; Abdullah, M.; Malik, T.; Yaseen, F.; Babar, Z.-U.-D. A systematic review of the economic burden of diabetes mellitus: Contrasting perspectives from high and low middle-income countries. J. Pharm. Policy Pract. 2024, 17, 2322107. [Google Scholar] [CrossRef] [Scilit]
  5. Hamilton, K.; Stanton-Fay, S.H.; Chadwick, P.M.; Lorencatto, F.; de Zoysa, N.; Gianfrancesco, C.; Taylor, C.; Coates, E.; Breckenridge, J.; Cooke, D. Sustained type 1 diabetes self-management: Specifying the behaviours involved and their influences. Diabet. Med. 2021, 38, e14430. [Google Scholar] [CrossRef] [Scilit]
  6. Powers, M.A.; Bardsley, J.; Cypress, M.; Duker, P.; Funnell, M.M.; Fischl, A.H.; Maryniuk, M.D.; Siminerio, L.; Vivian, E. Diabetes self-management education and support in type 2 diabetes: A joint position statement of the American Diabetes Association, the American Association of Diabetes Educators, and the Academy of Nutrition and Dietetics. Clin. Diabetes 2016, 34, 70–80. [Google Scholar] [CrossRef] [Scilit]
  7. Chrvala, C.A.; Sherr, D.; Lipman, R.D. Diabetes self-management education for adults with type 2 diabetes mellitus: A systematic review of the effect on glycemic control. Patient Educ. Couns. 2016, 99, 926–943. [Google Scholar] [CrossRef] [Scilit]
  8. Johnson, D.; Deterding, S.; Kuhn, K.-A.; Staneva, A.; Stoyanov, S.; Hides, L. Gamification for health and wellbeing: A systematic review of the literature. Internet Interv. 2016, 6, 89–106. [Google Scholar] [CrossRef] [Scilit]
  9. Fanaroff, A.C.; Patel, M.S.; Chokshi, N.; Coratti, S.; Farraday, D.; Norton, L.; Rareshide, C.; Zhu, J.; Klaiman, T.; Szymczak, J.E. Effect of gamification, financial incentives, or both to increase physical activity among patients at high risk of cardiovascular events: The BE ACTIVE randomized controlled trial. Circulation 2024, 149, 1639–1649. [Google Scholar] [CrossRef] [Scilit]
  10. Cheng, L.; Sit, J.W.; Choi, K.C.; Chair, S.Y.; Li, X.; He, X. Effectiveness of interactive self-management interventions in individuals with poorly controlled type 2 diabetes: A meta-analysis of randomized controlled trials. Worldviews Evid.-Based Nurs. 2017, 14, 65–73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Shiau, C.W.C.; Lim, S.M.; Cheng, L.J.; Lau, Y. Effectiveness of game-based self-management interventions for individuals with diabetes: A systematic review and meta-analysis of randomized controlled trials. Games Health J. 2021, 10, 371–382. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Patel, M.S.; Small, D.S.; Harrison, J.D.; Hilbert, V.; Fortunato, M.P.; Oon, A.L.; Rareshide, C.A.; Volpp, K.G. Effect of behaviorally designed gamification with social incentives on lifestyle modification among adults with uncontrolled diabetes: A randomized clinical trial. JAMA Netw. Open 2021, 4, e2110255. [Google Scholar] [CrossRef] [Scilit]
  13. Vas, A.; Devi, E.S.; Vidyasagar, S.; Acharya, R.; Rau, N.R.; George, A.; Jose, T.; Nayak, B. Effectiveness of self-management programmes in diabetes management: A systematic review. Int. J. Nurs. Pract. 2017, 23, e12571. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
  15. Haddaway, N.R.; Grainger, M.J.; Gray, C.T. Citationchaser: A tool for transparent and efficient forward and backward citation chasing in systematic searching. Res. Synth. Methods 2022, 13, 533–545. [Google Scholar] [CrossRef] [Scilit]
  16. Covidence. Covidence Systematic Review Software. Available online: https://www.covidence.org (accessed on 25 November 2025).
  17. Yao, W.; Han, Y.; Yang, L.; Chen, Y.; Yan, S.; Cheng, Y. Electronic Interactive Games for Glycemic Control in Individuals with Diabetes: Systematic Review and Meta-Analysis. JMIR Serious Games 2024, 12, e43574. [Google Scholar] [CrossRef] [Scilit]
  18. Ossenbrink, L.; Haase, T.; Timpel, P.; Schoffer, O.; Scheibe, M.; Schmitt, J.; Deckert, S.; Harst, L. Effectiveness of digital health interventions containing game components for the self-management of type 2 diabetes: Systematic review. JMIR Serious Games 2023, 11, e44132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Brady, V.J.; Mathew Joseph, N.; Ju, H.-H. Impact of gaming (gamification) on diabetes self-care behaviors and glycemic outcomes among adults with type 2 diabetes. Sci. Diabetes Self-Manag. Care 2023, 49, 493–511. [Google Scholar] [CrossRef] [Scilit]
  20. Lim, Y.S.; Ho, B.; Goh, Y.S. Effectiveness of game-based exercise interventions on modifiable cardiovascular risk factors of individuals with type two diabetes mellitus: A systematic review and meta-analysis. Worldviews Evid.-Based Nurs. 2023, 20, 377–400. [Google Scholar] [CrossRef] [Scilit]
  21. Kaihara, T.; Intan-Goey, V.; Scherrenberg, M.; Falter, M.; Frederix, I.; Akashi, Y.; Dendale, P. Impact of gamification on glycaemic control among patients with type 2 diabetes mellitus: A systematic review and meta-analysis of randomized controlled trials. Eur. Heart J. Open 2021, 1, oeab030. [Google Scholar] [CrossRef] [Scilit]
  22. Martos-Cabrera, M.B.; Membrive-Jiménez, M.J.; Suleiman-Martos, N.; Mota-Romero, E.; Cañadas-De la Fuente, G.A.; Gómez-Urquiza, J.L.; Albendín-García, L. Games and health education for diabetes control: A systematic review with meta-analysis. Healthcare 2020, 8, 399. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Christensen, J.; Valentiner, L.S.; Petersen, R.J.; Langberg, H. The effect of game-based interventions in rehabilitation of diabetics: A systematic review and meta-analysis. Telemed. e-Health 2016, 22, 789–797. [Google Scholar] [CrossRef] [Scilit]
  24. Kerfoot, B.P.; Gagnon, D.R.; McMahon, G.T.; Orlander, J.D.; Kurgansky, K.E.; Conlin, P.R. A team-based online game improves blood glucose control in veterans with type 2 diabetes: A randomized controlled trial. Diabetes Care 2017, 40, 1218–1225. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Kempf, K.; Martin, S. Autonomous exercise game use improves metabolic control and quality of life in type 2 diabetes patients-a randomized controlled trial. BMC Endocr. Disord. 2013, 13, 57. [Google Scholar] [CrossRef] [Scilit]
  26. Shea, B.J.; Reeves, B.C.; Wells, G.; Thuku, M.; Hamel, C.; Moran, J.; Moher, D.; Tugwell, P.; Welch, V.; Kristjansson, E. AMSTAR 2: A critical appraisal tool for systematic reviews that include randomised or non-randomised studies of healthcare interventions, or both. BMJ 2017, 358, j4008. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Smith, V.; Devane, D.; Begley, C.M.; Clarke, M. Methodology in conducting a systematic review of systematic reviews of healthcare interventions. BMC Med. Res. Methodol. 2011, 11, 15. [Google Scholar] [CrossRef] [Scilit]
  28. Thomson, D.; Russell, K.; Becker, L.; Klassen, T.; Hartling, L. The evolution of a new publication type: Steps and challenges of producing overviews of reviews. Res. Synth. Methods 2010, 1, 198–211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Pieper, D.; Antoine, S.-L.; Mathes, T.; Neugebauer, E.A.; Eikermann, M. Systematic review finds overlapping reviews were not mentioned in every other overview. J. Clin. Epidemiol. 2014, 67, 368–375. [Google Scholar] [CrossRef] [Scilit]
  30. Dichev, C.; Dicheva, D. Gamifying education: What is known, what is believed and what remains uncertain: A critical review. Int. J. Educ. Technol. High. Educ. 2017, 14, 9. [Google Scholar] [CrossRef] [Scilit]
  31. Deterding, S.; Dixon, D.; Khaled, R.; Nacke, L. From game design elements to gamefulness: Defining “gamification”. In Proceedings of the 15th International Academic MindTrek Conference: Envisioning Future Media Environments; Association for Computing Machinery: New York, NY, USA, 2011; pp. 9–15. [Google Scholar] [CrossRef] [Scilit]
  32. Hoffmann, A.; Christmann, C.A.; Bleser, G. Gamification in stress management apps: A critical app review. JMIR Serious Games 2017, 5, e7216. [Google Scholar] [CrossRef] [Scilit]
  33. Priesterroth, L.; Grammes, J.; Holtz, K.; Reinwarth, A.; Kubiak, T. Gamification and behavior change techniques in diabetes self-management apps. J. Diabetes Sci. Technol. 2019, 13, 954–958. [Google Scholar] [CrossRef] [Scilit]
  34. Lasserson, T.J.; Thomas, J.; Higgins, J.P. Starting a review. In Cochrane Handbook for Systematic Reviews of Interventions; John Wiley & Sons: Hoboken, NJ, USA, 2019; pp. 1–12. [Google Scholar] [CrossRef] [Scilit]
  35. Sideri, S.; Papageorgiou, S.N.; Eliades, T. Registration in the international prospective register of systematic reviews (PROSPERO) of systematic review protocols was associated with increased review quality. J. Clin. Epidemiol. 2018, 100, 103–110. [Google Scholar] [CrossRef] [Scilit]
  36. Tawfik, G.M.; Giang, H.T.N.; Ghozy, S.; Altibi, A.M.; Kandil, H.; Le, H.-H.; Eid, P.S.; Radwan, I.; Makram, O.M.; Hien, T.T.T. Protocol registration issues of systematic review and meta-analysis studies: A survey of global researchers. BMC Med. Res. Methodol. 2020, 20, 213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Lundh, A.; Lexchin, J.; Mintzes, B.; Schroll, J.B.; Bero, L. Industry sponsorship and research outcome. Cochrane Database Syst. Rev. 2017, 2, 3R00033. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Faggion, C., Jr.; Atieh, M.; Zanicotti, D. Reporting of sources of funding in systematic reviews in periodontology and implant dentistry. Br. Dent. J. 2014, 216, 109–112. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Jefferson, T. Sponsorship bias in clinical trials: Growing menace or dawning realisation? J. R. Soc. Med. 2020, 113, 148–157. [Google Scholar] [CrossRef] [Scilit]
  40. Kakazu, V.A.; Assis, M.; Bacelar, A.; Bezerra, A.G.; Ciutti, G.L.R.; Conway, S.G.; Galduróz, J.C.F.; Drager, L.F.; Khoury, M.P.; Leite, I.P.A. Industry sponsorship bias in randomized controlled trials of digital cognitive behavioral therapy for insomnia: A meta-research study based on the 2023 Brazilian guidelines on the diagnosis and treatment of insomnia in adults. Front. Neurol. 2025, 16, 1600767. [Google Scholar] [CrossRef] [Scilit]
Figure 1. PRISMA flowsheet for the systematic review of systematic reviews.
Diabetology 07 00111 g001
Table 1. Descriptive characteristics of included studies.
Author (Year)Number of
Included Studies
Design of
Individual Studies
Participants (General
Characteristics)
InterventionOutcomes (Measurable)
1Yao et al. 2024 [17]9 studies7 RCTs (Randomized Controlled Trials), 2 non-RCTs913 participants with 747 cases of T2DM. Two studies were from Europe, three from Asia, and four from North America. Video games, smartphone games, digital handheld games, gamified behavior/education systems
  • HbA1c, fasting blood glucose FBG, physical activity, weight, total cholesterol, LDL-C, HDL-C, triglycerides
2Ossenbrink et al. 2023 [18]10 studies All studies were RCTThe number of male and female participants were 1061 and 533, respectively. The overall range of sample size was 8 to 465 participants. Four studies were from North America, four from Europe, one from Asia and one from Australia. Exergames, serious games (education), gamified self-management apps, story-based fitness games, hybrid/multicomponent (self-management apps with game elements)
  • Clinical parameters like blood glucose levels, BMI, and BP
  • Patient-reported outcomes such as physical activity or dietary behavior, self-efficacy, empowerment, and quality of life
3Brady et al. 2023 [19]9 studies5 RCTs, and 4 were quasi-experimental studiesA total of 1370 participants were enrolled with sample sizes ranging from 10 to 456. Four studies were conducted in North America, four in Europe, and one in Australia.Exergames, smartphone apps, cognitive/educational games
  • Changes in HbA1c, weight loss, changes in BMI, body fat percentage, BP, total cholesterol, and HDL
  • Foot care, changes in self-reported efficacy or quality of life, eating habits, physical activity, self-monitoring of blood glucose
4Lim et al. 2023 [20]11 studies All of the studies were RCTThis review included 1045 individuals with sample sizes ranging between 20 and 361. Two studies were conducted in North America, three in Asia, five in Europe, and one was conducted in both USA and Qatar. Gamified apps, exergames, sensor-based technologies
  • HbA1c, blood pressure, LDL-c
  • Quality of life, physical activity levels
5Shiau et al. 2021 [11]13 studiesAll studies were RCT1195 individuals with diabetes from 1997 to 2019 in North America (6), Europe (4), and Asia (3). Trials were conducted among individuals with type 1 diabetes, type 2 diabetes, or both. Sample sizes ranged from 24 to 456.Video games, mobile games, VR, gamified education
  • Changes in HbA1c
  • Changes in “physical activity, balance, and fall efficacy”, “diabetes knowledge and self-efficacy”
6Kaihara et al. 2021 [21]3 studiesAll studies were RCTA total of 704 patients were included in the three RCTs. One study was from Europe and two were from North America. The rate of male participants and mean ages of participants ranged from 46% to 94% and 60 to 63 years, respectively. The sample size ranged from 120 to 456. Baseline characteristics were not significantly different between the intervention group and the control group. Diagnosis of patients included only T2DM. Gamified education and exergames
  • Changes in HbA1c
  • Mean daily step counts
7Cabrera et al. 2020 [22]10 studies, 4 included in meta-analysis7 RCT, 1 pilot quasi-experimental study, 1 case and control study, 1 cohort study70% of the studies were randomized clinical trials, 10% cohort studies, 10% cases and controls studies, and 10% qualitative studies. Most of the studies were performed in North America (70%) and other studies were performed in Europe. The higher sample was n = 456 and the lower n = 20. 40% of the studies were centered on people with DM1.Video games, mobile games, exergames, online games, gamified education, and motivational games
  • Changes in HbA1c
8Christensen et al. 2016 [23]4 studiesAll studies were RCTTwo studies were from North America, one from Asia and one from Europe. Video games, exergames (one with diabetes education and one without), serious game
  • Changes in HbA1c
  • Health-related quality of life, diabetes-related knowledge, balance, and strength
Table 2. Critical appraisal of included studies using AMSTAR2.
ItemsCriteriaYao et al.
2024 [17]
Ossenbrink et al.
2023 [18]
Brady et al. 2023 [19]Lim et al.
2023 [20]
Shiau et al.
2021 [11]
Kaihara et al.
2021 [21]
Cabrera et al.
2020 [22]
Christensen et al.
2016 [23]
1Did the research questions and inclusion criteria for the review include the components of PICO?YYYYYYYY
2Did the report of the review contain an explicit statement that the review methods were established prior to the conduct of the review, and did the report justify any significant deviations from the protocol?NYYYYNNN
3Did the review authors explain their selection of the study designs for inclusion in the review?YYYYYYYY
4Did the review authors use a comprehensive literature search strategy?YYYYYYYY
5Did the review authors perform study selection in duplicate?YYYYNYYY
6Did the review authors perform data extraction in duplicate?YYYYYNNY
7Did the review authors provide a list of excluded studies and justify the exclusions?YYYYYYYY
8Did the review authors describe the included studies in adequate detail?YYYYYYYY
9Did the review authors use a satisfactory technique for assessing the risk of bias (RoB) in individual studies that were included in the review?YYYYYYNY
10Did the review authors report on the sources of funding for the studies included in the review?NNNNNNNN
13Did the review authors account for RoB in primary studies when interpreting/discussing the results of the review?NYYYYYNY
14Did the review authors provide a satisfactory explanation for, and discussion of, any heterogeneity observed in the results of the review?YNYYYYNY
16Did the review authors report any potential sources of conflict of interest, including any funding they received for conducting the review?YYNYYYYY
% of items meeting the criteria76.9%84.6%84.6%92.3%84.6%76.9%53.8%84.6%
Table 3. Detailed description of outcomes in each study.
StudyBlood Glucose and HbA1c OutcomesChange in Confidence and Knowledge Regarding Diabetes
Management
Yao et al. 2024 [17]HbA1C
Meta-analysis involving seven studies revealed improvement in HbA1c in intervention group; however, the improvement was not significant (MD = −0.09%, 95% CI: −0.29, 0.10, p: 0.36).
Blood glucose
A meta-analysis was performed using three studies. Gamification resulted in reduction in FBG level in intervention group; however, the reduction was not significant (MD: −0.94, 95% CI: −9.34, 7.46, p: 0.55).
Ossenbrink et al. 2023 [18]HbA1C
6/10 studies analyzed HbA1c. Out of six, two studies had significant results in terms of reduction and between group differences both post intervention and after following up.
First study: Kerfoot et al. [24]: Baseline levels, IG: 9.01 (CI 8.83,9.2), CG: 8.92 (CI 8.74, 9.1). Post-intervention levels, IG: 8.28 (CI 8.01, 8.46), CG: 8.46 (CI 8.28, 8.74). After 48 weeks: IG: −2.88, CG: −2.61 (p = 0.048 between groups).
Second study: Kempf and Martin [25]: Baseline levels, IG: 7.1(SD 1.3), CG: 6.8 (SD 0.9). Post-intervention levels, IG: 6.8 (SD 1.0), CG: 6.7 (SD 0.7). After 12 weeks: IG: −0.3 (p < 0.001 between groups).
Blood glucose
Fasting plasma glucose (FPG) level: Evaluated by 2/10 studies. Only one out of two had significant results. Kempf and Martin [25]: A significant decrease in FPG was noted in both intervention and control groups and p value for intergroup differences was 0.008.
Only one study assessed health literacy. A positive effect of gamification was found in knowledge regarding diet for patients with diabetes (p = 0.001).
Brady et al. 2023 [19]HbA1C
6/9 (66.7%) studies used HbA1c as the outcome measure. Five out of six studies had a reduction in the outcome measure; however, only two studies had a significant reduction in HbA1c. Kerfort et al. [24] and Kempf and Martin [25] as described in Ossenbrink et al. [18] were the studies with significant reduction.
Lim et al. 2023 [20]HbA1C
Five studies were pooled for meta-analysis. A minimal effect size was noted for game-based exercise intervention on HbA1c; however, it was not significant (d = −0.16, 95% CI −0.45, 0.14, Z = 1.05, p = 0.29).
Shiau et al. 2021 [11]HbA1c
HbA1c levels at post intervention were used as the outcomes by seven [of 12; 58.33%] RCTs. A comparison between intervention and control groups showed no difference in patients’ levels of HbA1c in post intervention (Z = 0.61, p = 0.54); the effect was extremely small (g = 0.06). A change in HbA1c was evaluated by three trials, whereas two trials evaluated HbA1c levels at follow-up assessments. The conducted meta-analyses exhibited significant improvement on patients’ levels of HbA1c (Z = 2.31, p = 0.02) with small effect (g = 0.18), thereby favoring game-based self-management interventions. However, the meta-analyses results failed to show significant differences between intervention and control groups for HbA1c levels at follow-up assessment.
Three trials assessed diabetes self-efficacy and knowledge scores. A non-significant difference in diabetes knowledge and self-efficacy scores was observed between intervention and control groups (Z = 0.76–0.99, p = 0.32–0.45).
Kaihara et al. 2021 [21]HbA1c
Three studies [of 3] described HbA1c. There was no significant heterogeneity in the studies, and all three studies showed a decreased HbA1c in the intervention group. HbA1c significantly decreased in the intervention group compared to the control group in the overall effect [mean difference −0.21%; 95% CI (−0.37 to −0.05); p = 0.01; I2 = 0%].
Cabrera et al. 2020 [22]HbA1c
Only four studies [40%] were included for the meta-analysis; 50% of the studies had samples with DM2. Meta-analysis demonstrated reduction in HbA1c in intervention group (the mean differences in the percentage of HbA1c was −0.12 [95% CI = −0.57, 0.33]), however the difference was not statistically significant.
Christensen et al. 2016 [23]HbA1c
HbA1c was reported by three [of four; 75%] studies. No significant treatment effect was found between game-based intervention and non-gaming intervention groups (SMD and 95% CI = −0.10 [−0.33, 0.14]), p = 0.4680.
Diabetes-related knowledge was tested in only one study. Participants were interviewed and given points based on how many questions they answered correctly. The difference between the game-based intervention group and the control group (p = 0.64) was not significant.
MD = mean difference, FBG = fasting blood glucose, CI = confidence interval, SMD = standard mean difference.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.