Review

Rewiring Resistance: Integrating TKIs, Dual Checkpoint Blockade, LRT, and Role of CAR-T After ICI Progression in HCC—A Narrative Review


by
Sai Sushrutha Mudupula Vemula
1,
Ahmed Abdelhakeem
2,
Umair Majeed
2,
Nirmal Onteddu
3 and
Osama M. MoSalem
4,*
1
Department of Internal Medicine, University of Michigan Health-Sparrow Hospital/Michigan State University, Lansing, MI 48912, USA
2
Department of Medicine, Division of Hematology-Oncology, Mayo Clinic, Jacksonville, FL 32224, USA
3
Department of Internal Medicine, College of Medicine, University of Florida, Jacksonville, FL 32209, USA
4
Department of Oncology, Saint Luke’s Cancer Institute, Kansas City, MO 64111, USA
*
Author to whom correspondence should be addressed.
Livers 2026, 6(5), 85; https://doi.org/10.3390/livers6050085
Submission received: 31 December 2025 / Revised: 2 April 2026 / Accepted: 7 August 2026 / Published: 28 August 2026

Abstract

Background/Objectives: Hepatocellular carcinoma (HCC) remains a leading cause of cancer mortality worldwide, due to poor prognosis and limited curative options in advanced stages. Though immune checkpoint inhibitor (ICI)-based combinations have been the first-line therapies, with higher survival compared to tyrosine kinase inhibitors (TKIs), most patients progress within six months and evidence-based guidance for subsequent therapy remains limited. This review summarizes second- and third-line treatment strategies after ICI failure, while highlighting critical research gaps and future advancements needed. Methods: We performed a comprehensive literature review of PubMed, Embase, Cochrane, and major conference proceedings (ASCO, ESMO, AASLD) up to August 2025, including retrospective cohorts, post hoc trial analyses, simulation models, and ongoing prospective trials on second-line therapy in patients with metastatic HCC who progressed on first-line therapy. Discussion and Conclusions: TKIs remain the most widely used second-line option after ICI failure. Lenvatinib, a multi-targeted TKI with strong VEGF inhibition, has shown higher progression-free survival (PFS) compared with sorafenib through tumor vasculature normalization and enhanced T cell infiltration. Other multi-targeted TKIs, like cabozantinib and regorafenib, have shown survival benefits in later line settings. In TKI-refractory or ineligible patients, treatment options are limited, and enrollment in clinical trials is recommended. Retrial of ICIs may be considered in highly selected patients, but evidence remains limited, and this approach is not standard. Concomitant locoregional therapies (LRTs) are useful in oligoprogression where systemic therapy is inadequate, but their integration with systemic therapy is underexplored, and no phase III trials yet define optimal sequencing post-ICI failure. Additionally, we describe novel therapeutic strategies such as chimeric antigen receptor T cell therapy (CAR-T) in HCC.

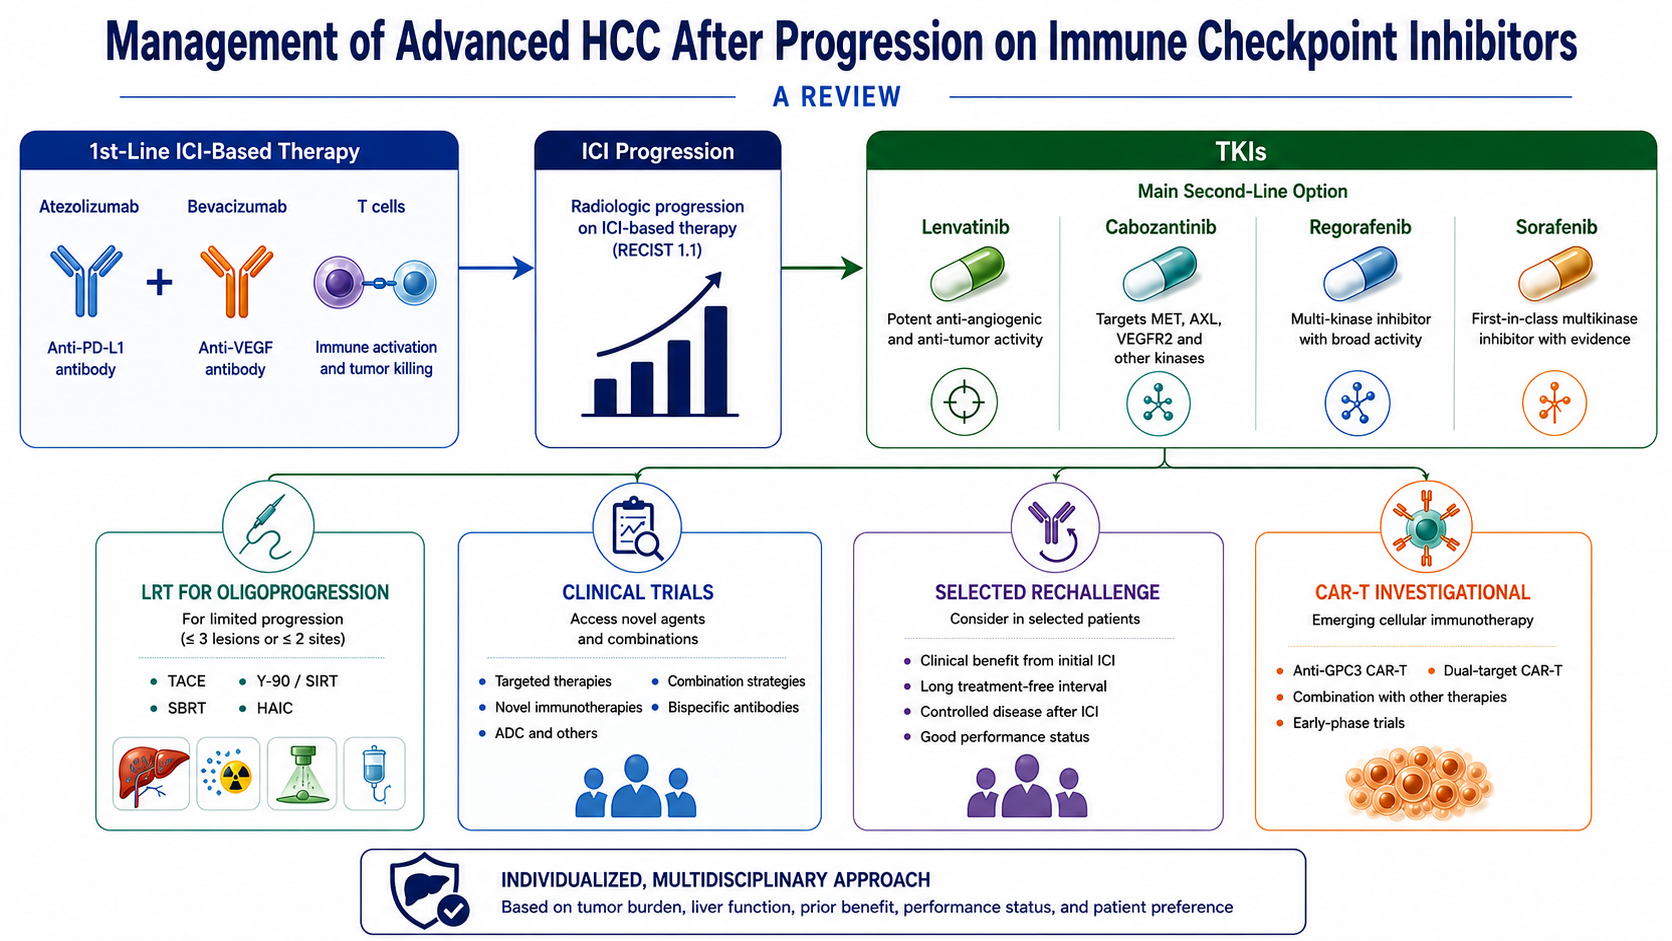
Graphical Abstract

1. Introduction

Hepatocellular carcinoma (HCC) is the most common primary liver cancer, accounting for 75–85% of cases, followed by intrahepatic cholangiocarcinoma (10–15%); it is the sixth most common cancer worldwide and the third leading cause of cancer-related death, with a five-year survival rate of approximately 15% [1,2]. In the United States, HCC incidence has tripled since 1980, and HCC-related mortality increased by 43% between 2000 and 2016 [3,4]. Most cases arise from chronic HBV, HCV, or alcohol-related liver disease, but MASLD, obesity, and metabolic syndrome are emerging as dominant risk factors, especially in Western countries [5]. Curative treatment options like surgical resection, transplant, and local ablation are often not feasible in patients with advanced hepatocellular carcinoma (HCC) due to poor functional reserve or the presence of distant metastases as a result of which current international guidelines recommend systemic therapy as the standard of care for these patients [6].
The management of HCC should be interpreted within the context of the Barcelona Clinic Liver Cancer (BCLC) staging system, liver functions and performance status. In patients with BCLC stage 0/A, most clinical practice guidelines recommend curative approaches such as surgical resection, thermal ablation or transplantation. Transarterial chemoembolization (TACE) and systemic therapies are preferred for patients with intermediate (BCLC B) and advanced (BCLC C) HCCs, respectively [7].
Locoregional therapy (LRT) is best suited for patients with early to intermediate HCC (BCLC stage A or B) whose tumors are confined to the liver without extrahepatic spread, have three or fewer lesions or multinodular disease without vascular invasion, and maintain good liver function (Child–Pugh A or early B) with ECOG performance status 0–1 and patent portal vein flow [7,8].

2. Materials and Methods

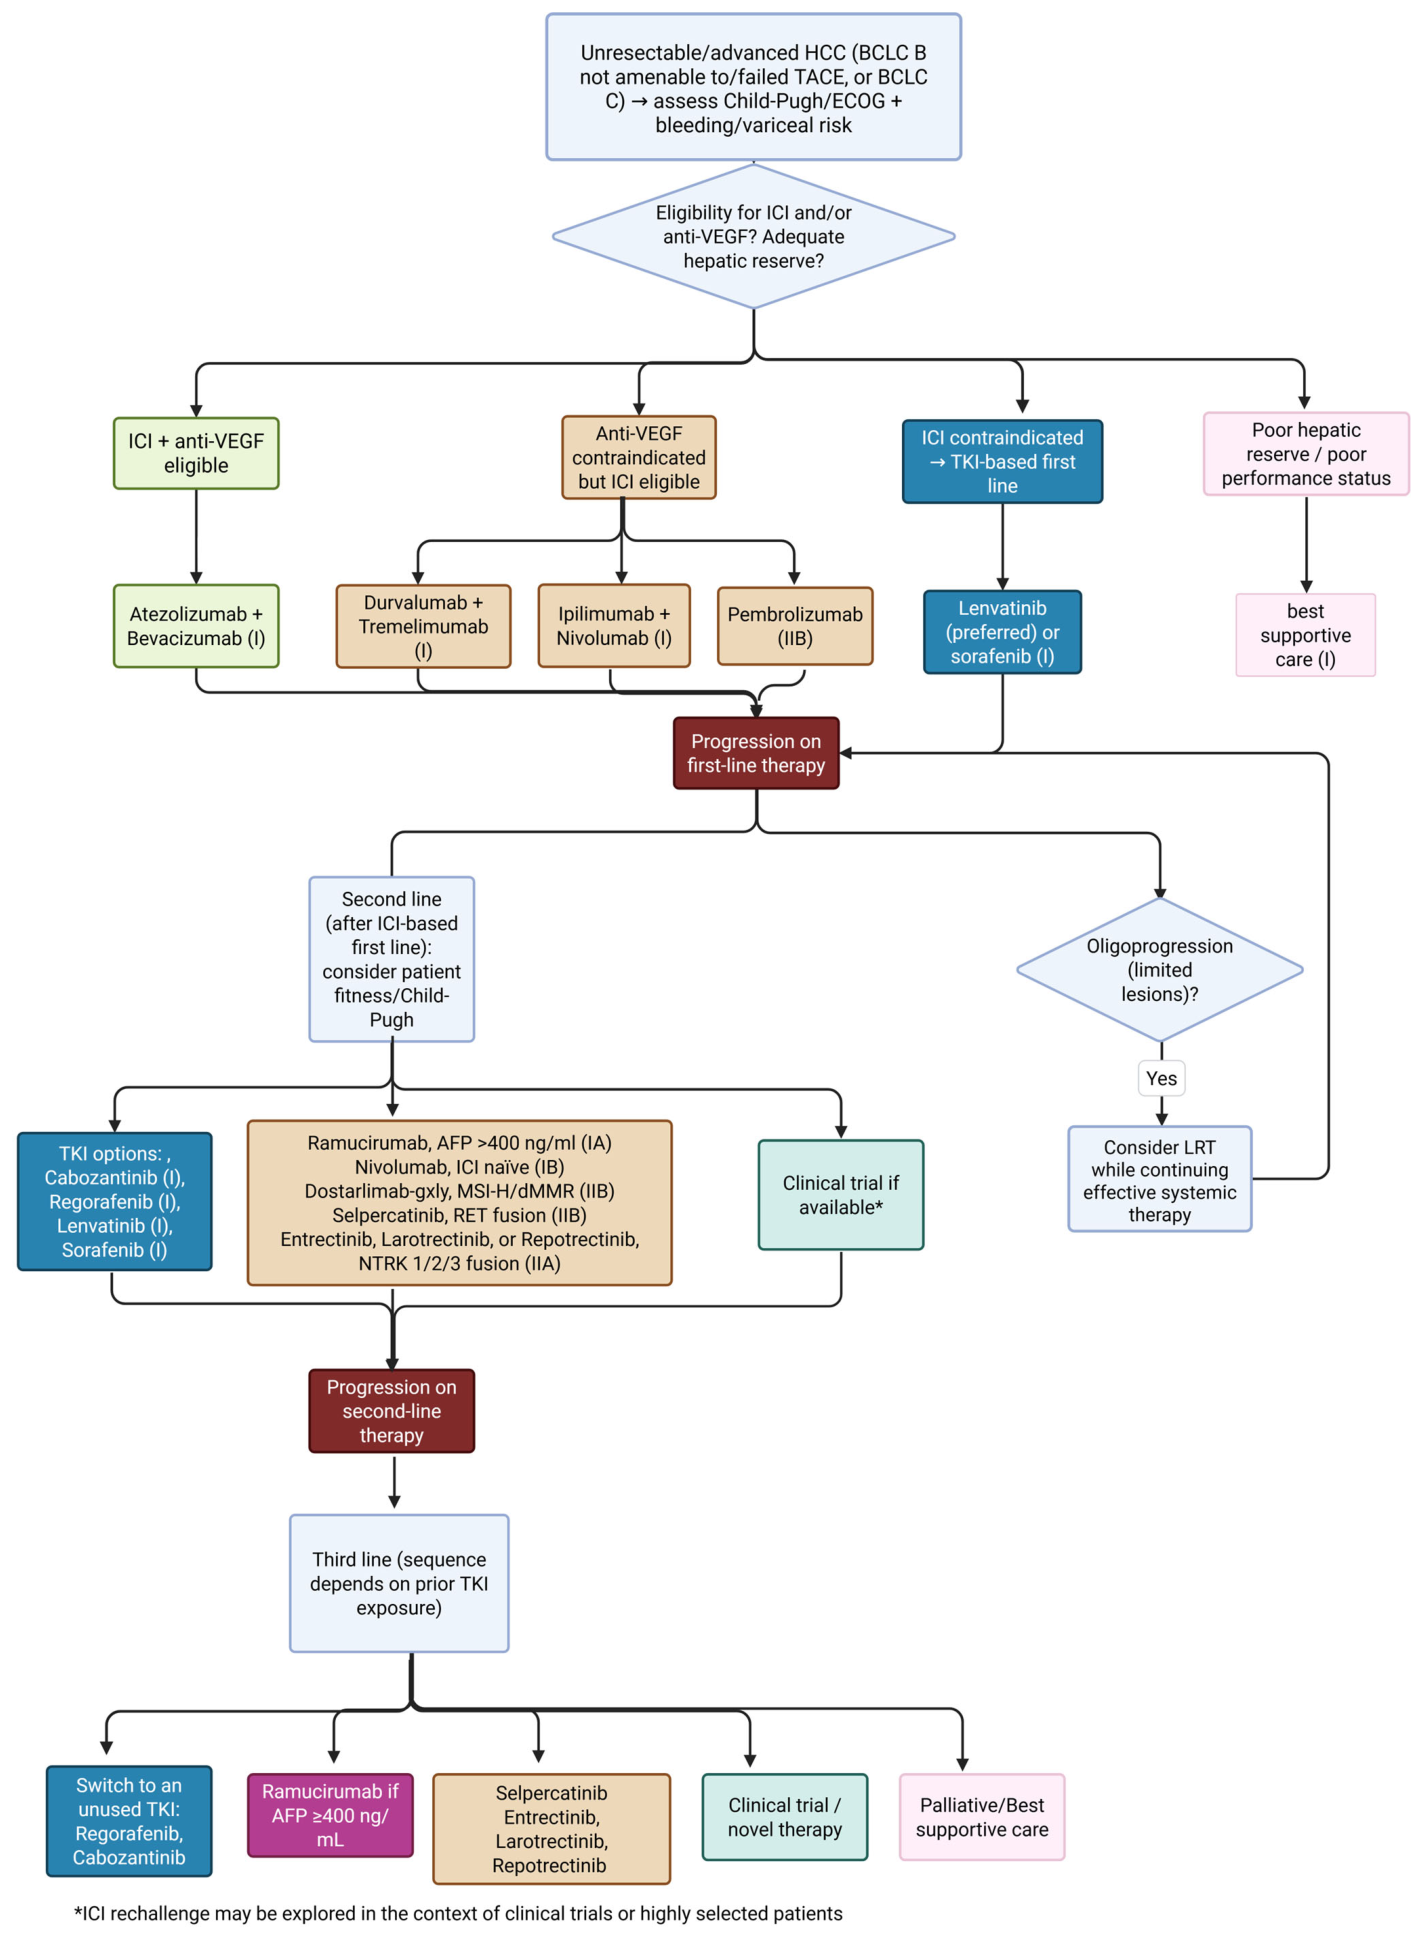
We performed a comprehensive literature review of PubMed, Embase, Cochrane, and major conference proceedings (ASCO, ESMO, AASLD) up to August 2025, including retrospective cohorts, post hoc trial analyses, simulation models, and ongoing prospective trials focusing on current guidelines on second-line treatment after failure on TKIs or ICIs as first-line therapy, with a recommended treatment algorithm for metastatic HCC including second-line therapy mentioned below in Figure 1.

3. Results and Discussion

3.1. First-Line Therapy

Immune checkpoint inhibitors (ICIs) have changed the therapeutic landscape for unresectable HCC. Guidelines on first-line therapy remain clear where immunotherapy with atezolizumab plus bevacizumab, durvalumab plus tremelimumab and most recently ipilimumab plus nivolumab are the mainstay of treatment in those who are eligible for immunotherapy [9].
In the IMBrave 150 trial, first-line therapy with atezolizumab (ICI) plus bevacizumab (Anti-VEGF) compared to tyrosine kinase inhibitors (TKIs) with sorafenib significantly improved OS (HR 0.66, 95% CI 0.52–0.85) and median PFS (6.9 vs. 4.3 months) in trials [10]. In patients with contraindications for anti-VEGF therapy like untreated high-risk varices, recent gastrointestinal (GI) bleed, uncontrolled hypertension (HTN), and heavy proteinuria, tremelimumab (a CTL4 inhibitor) plus durvalumab (a PDL1 inhibitor) is recommended due to high sustained OS (16.4 vs. 13.8 months, HR-0.78) compared to sorafenib alone with durvalumab monotherapy being non-inferior to sorafenib alone per the HIMALAYA trial [11]. In the CheckMate 040 study with a 5-year follow-up, patients with sorafenib-treated advanced HCC were randomized into three arms evaluating different combinations of nivolumab and ipilimumab: Arm A (nivolumab plus higher-dose ipilimumab), Arm B (nivolumab plus lower-dose ipilimumab), and Arm C (nivolumab given more frequently with low-dose ipilimumab). The overall response rates were 34%, 27%, and 29% in Arms A, B, and C, respectively, with median durations of response of 51.2, 15.2, and 21.7 months. Median overall survival was 22.2, 12.5, and 12.7 months, with 5-year overall survival rates of 29%, 19%, and 21%, demonstrating the greatest long-term benefit in Arm A [9]. The combination of camrelizumab plus rivoceranib was approved as first-line therapy for unresectable hepatocellular carcinoma based on the phase 3 CARES-310 study; the regimen showed a median progression-free survival of 5.6 months compared with 3.7 months for sorafenib and a median overall survival of 22.1 months versus 15.2 months, demonstrating a clear clinical benefit [12].
The COSMIC-312 trial, which compared cabozantinib plus atezolizumab versus sorafenib, showed improved PFS (6.8 months in the combination arm versus 4.2 months in the sorafenib-only arm; p = 0·0012); however, there was no statistically significant difference between the two arms with OS of 15.4 months vs. 15.5 months respectively (HR 0.90; p = 0.44) [13]. The phase 3 LEAP-002 trial compared lenvatinib plus pembrolizumab to lenvatinib monotherapy as first-line therapy for unresectable HCC (Child–Pugh A). Median OS was 21.2 vs. 19.0 months (HR 0.84; p—0.023) and PFS was 8.2 vs. 8.0 months (HR 0.87; p—0.047), showing numerical but not statistically significant improvements. The combination did not meet prespecified efficacy thresholds and therefore does not support changing current first-line practice in advanced HCC [14].
TKIs are preferred in patients in whom ICIs and anti-vascular endothelial growth factors (anti-VEGFs) are contraindicated, with lenvatinib being the first choice with OS noninferior to sorafenib with higher PFS and ORR vs. sorafenib per the REFLECT trial [15]. The phase 3 RATIONALE-301 trial compared tislelizumab with sorafenib as first-line therapy for unresectable HCC in 674 patients (BCLC B/C, Child–Pugh A) where tislelizumab achieved a noninferior OS (15.9 vs. 14.1 months; HR 0.85), with higher objective response rate (14.3% vs. 5.4%) and longer duration of response (36.1 vs. 11.0 months). Progression-free survival was similar (2.1 vs. 3.4 months). Grade ≥ 3 adverse events were lower with tislelizumab (22.2% vs. 53.4%), and quality-of-life outcomes were better. These findings support tislelizumab as an effective, first-line alternative for patients ineligible for VEGF-based therapy [16]; however, this regimen is still investigational and yet to receive FDA approval.
Despite this, the majority of HCC patients will progress on first-line therapy and evidence-based guidance for subsequent therapy remains limited. Current decisions are mostly based on empirical practice, retrospective studies, and early-phase trial data. In this review, we aim to expand on the second-line therapeutic approaches after ICI failure, focusing on TKIs, immunotherapy rechallenge with mono/dual or combination therapy with VEGF inhibitors, and concomitant locoregional therapies (LRTs), while highlighting critical research gaps and future advancements needed.

3.2. Hyperprogressive Disease in HCC, Supportive Care vs. Second-Line Systemic Therapy and Indications for Second-Line Treatment

In hepatocellular carcinoma, hyperprogressive disease (HPD) is defined as the paradoxical occurrence of accelerated tumor growth following immunotherapy, and is defined by 3-dimensional tumor volume (TGR) ratio > 4, 2-dimensional tumor diameter ratio > 4, or absolute TGR increase ≥40%, and occurs in approximately 10–15% of patients [17]. This has been associated with a high neutrophil lymphocyte ratio (NLR) > 6, older age, and baseline tumor biology [18]. Mechanisms of action include PD-1/PD-L1 blockade, which may expand or activate regulatory T cells (Tregs), enhancing immunosuppressive effects, while checkpoint inhibition can skew macrophages toward an M2 phenotype, fostering angiogenesis and tumor growth, and antibody Fc domains may engage Fcγ receptors on myeloid cells, promoting pro-tumor inflammatory pathways [19]. HPD status is independently a poor prognostic factor with shorter overall survival [20].
In addition, not all patients would be candidates for second-line therapy post-ICI failure and careful evaluation is recommended. Patients with poor hepatic reserve (Child–Pugh C, and Advanced Child–Pugh B ≥ B8/B9), particularly with the presence of jaundice, refractory ascites, hepatic encephalopathy, poor performance status (ECOG ≥ 2), severe comorbidities or organ dysfunction like decompensated heart failure, uncontrolled hypertension, recent stroke/MI, severe renal impairment (GFR < 30 for TKIs), active major bleeding or high bleeding risk (uncontrolled varices), uncontrolled autoimmune disease, severe immune-related adverse events, and symptomatic progression with multiorgan failure, are less likely to derive benefit from additional systemic therapies. In such settings, best supportive care is favored over continuing with second-line therapy.
Overall, evidence supporting treatment beyond first-line atezolizumab and bevacizumab is largely derived from retrospective and real-world data [21]. In a multinational international retrospective cohort study of 406 patients progressing on first-line atezolizumab–bevacizumab, continued active systemic therapy significantly improved post-progression survival versus best supportive care (9.7 vs. 2.6 months; HR 0.41, p < 0.001). Favorable prognostic factors included ECOG < 2, absence of portal vein tumor thrombus, and continuing systemic second-line therapy indicative of better PPS [21]. In another international observational study with 604 metastatic HCC patients on ICIs, 60% developed HPD with a median PPS (median time a patient survives after their disease has worsened following a treatment to assess outcomes after progression and the impact of subsequent therapies on overall survival) of 5.3 months. Intrahepatic growth and new vascular invasion predicted worse survival outcomes, and continuation of ICI beyond radiologic disease progression was strongly associated with improved post-progression survival. Patients who received ICI beyond PD in combination with a subsequent TKI had the greatest benefit (HR 0.17, 95% CI 0.09–0.32, p < 0.0001), while those who continued ICI without a TKI also showed significantly prolonged survival compared to no therapy (HR 0.39, 95% CI 0.26–0.58, p < 0.0001) [22]. Overall, the optimal sequencing strategy following ICI-based first-line therapy remains undefined and prospective randomized trials are lacking but patient selection and careful evaluation remain crucial to ensure tolerance to subsequent therapies.

3.3. Tyrosine Kinase Inhibitors as Second-Line Therapy in Metastatic HCC

Tyrosine kinase inhibitors like lenvatinib, sorafenib, regorafenib, and cabozantinib mediate VEGF blockade, normalizing aberrant tumor vasculature, improve perfusion, reduce hypoxia, reduce tumor-associated macrophages, and promote CD8+ T cell infiltration through enrichment of type I IFN signaling, thereby enhancing PD-(L)1 activity as seen with atezolizumab–bevacizumab [23]. AXL overexpression in solid tumors promotes TKI resistance and causes an immunosuppressive phenotype by impairing antigen presentation and fostering suppressive immune cell infiltration. Its inhibition restores innate immune signaling and resensitizes tumors to both TKI and PD-1 blockade [24]. Similarly, activation of the WNT–β-catenin pathway creates an “immune-excluded” or “cold tumor” microenvironment by preventing T cell infiltration, explaining the poor response of these tumors to ICIs [25]. Lenvatinib inhibits VEGFR1-3, FGFR1-4 (notably FGFR4), PDGFRα, RET, KIT, and AXL, and similarly causes vascular normalization and immune modulatory effects, counteracting this immune exclusion as described above, and augmenting anti-PD-1 efficacy via NRP-1/PDGFRβ signaling and suppression of PD-L1/Treg induction through FGFR4 blockade. High FGFR4 expression or serum FGF19 levels have been associated with greater lenvatinib responsiveness, underscoring the FGF19-FGFR4 axis as a predictive biomarker [26]. The association between FGFR4/FGF19 expression and lenvatinib responsiveness, while biologically compelling, requires prospective validation in biomarker-enriched trials before clinical application.
In a multicenter, single-arm phase II clinical trial, Hyung-Don Kim et al. evaluated second-line therapy with lenvatinib in 50 patients with unresectable HCC and Child–Pugh A liver function who progressed after first-line atezolizumab and bevacizumab in which lenvatinib showed promising efficacy as second-line therapy in unresectable HCC with a median PFS and OS of 5.4 and 9.8 months, respectively [27]. In a large multicenter retrospective study, lenvatinib showed better PFS (3.5 vs. 1.8 months, p—0.001) and comparable OS to sorafenib in patients with unresectable HCC after atezolizumab plus bevacizumab failure [28]. The majority of patients (72.2%) in the study had Child–Pugh A liver function [28]. In the Markov analysis of post-atezolizumab plus bevacizumab sequences, treatment with lenvatinib yielded the longest survival (median OS—24 months, LYG 0.50), closely followed by sorafenib (median OS of 23 months, LYG 0.42). Atezolizumab plus bevacizumab followed by sorafenib showed the safest profile (SAEs 63%) [29]. Based on those results, lenvatinib is currently approved by the FDA as a treatment option after progression on ICIs or in the first line for those who are not candidates for ICIs, as mentioned in Table 1.
Cabozantinib, a multi-targeted TKI against VEGF, MET and AXL, is an FDA-approved second- or later line treatment option for metastatic or advanced HCC. In the phase III CELESTIAL trial, cabozantinib was evaluated in patients with HCC and Child–Pugh A liver function who had disease progression on sorafenib. Cabozantinib improved OS (10.2 months vs. 8.0 months respectively, HR 0.76) and PFS (median 5.2 months vs. 1.9 months respectively, HR 0.44), confirming cabozantinib as an effective second-line treatment option for previously treated HCC [30]. Storandt, M. H. et al. showed a median PFS of 2.1 months and median OS of 7.7 months in patients with cabozantinib [31]. A multicenter phase II trial showed a median PFS and OS of 4.3 (95% CI 3.3–6.7) and 14.3 (95% CI 8.9-NR) months, respectively, in patients on cabozantinib and Child–Pugh A when used as a second-line therapy, as mentioned in Table 1 [32].
In a single-arm phase II study by Cheon et al., regorafenib was evaluated as second-line therapy after atezolizumab–bevacizumab failure in unresectable HCC, and Child–Pugh A liver function that showed a median PFS of 3.5 months and OS of 10.5 months; ORR and disease control rates were 10% and 82.5%, respectively, with grade 3/4 adverse events being infrequent [33]. In a phase 3, randomized, placebo-controlled trial, a total of 843 patients with advanced hepatocellular carcinoma who had previously progressed on sorafenib were screened, and a majority were enrolled and randomized to receive either regorafenib or placebo. Eligible patients had preserved liver function, good performance status, and adequate hematologic and organ function. Patients with longer time to progression on prior sorafenib showed better outcomes, including OS of 15.0 vs. 3.6 months (p < 0.001), higher ORR (13.3% vs. 0%, p—0.009), and a trend toward improved PFS (3.8 vs. 2.5 months, p—0.054) with regorafenib demonstrating meaningful efficacy and acceptable safety as a second-line option, aligning with results from the RESORCE trial [34], with all the above trials mentioned in Table 1. Based on this, the FDA has approved regorafenib for patients with advanced HCC and preserved liver function who had disease progression on sorafenib.
Table 1. Tyrosine kinase inhibitors as second-line therapy in metastatic HCC.
Study/TrialStudy DesignStudy Population/FocusKey Results
Hyung-Don Kim et al. [27].Multicenter, single-arm studyPatients with advanced HCC progressing after first-line atezolizumab–bevacizumab treated with second-line lenvatinibmPFS 5.4 months (95% CI 4.2–7.1); mOS 9.8 months (95% CI 8.1-NR); ORR 14.0%; DCR 82.0%.
Chon et al. [28].Multicenter, retrospective studyPatients receiving second-line sorafenib or lenvatinib after progression on atezolizumab–bevacizumabORR similar between lenvatinib and sorafenib (5.6% vs. 8.3%; p = 0.643); DCR higher with lenvatinib (66.7% vs. 22.2%; p < 0.001); PFS improved with lenvatinib (3.5 vs. 1.8 months; p = 0.001); OS not significantly different (10.3 vs. 7.5 months; p = 0.353).
Storandt et al. [31].Multicenter, retrospective analysisPatients with HCC progressing on first-line immunotherapy treated with cabozantinibmPFS 2.1 months (95% CI 1.3–3.9); mOS 7.7 months (95% CI 5.3–14.9) from cabozantinib initiation.
Markov model analysisDecision-analytic modeling studyModeled sequences of atezolizumab–bevacizumab followed by second-line TKIs (sorafenib, lenvatinib, regorafenib, cabozantinib, ramucirumab)Atezolizumab–bevacizumab followed by lenvatinib (mOS 24 months) or sorafenib (mOS 23 months) yielded greatest life-years gained (0.50 and 0.42 years); atezolizumab–bevacizumab to sorafenib was the safest sequence (serious AEs 63%).
CELESTIAL TrialRandomized, double-blind, phase 3 trialPreviously treated advanced HCC after TKI/ICI exposure: cabozantinib vs. placebomOS 10.2 vs. 8.0 months (HR 0.76; 95% CI 0.63–0.92; p = 0.005); mPFS 5.2 vs. 1.9 months (HR 0.44; p < 0.001); ORR 4% vs. <1% (p = 0.009); grade ≥ 3 AEs 68% vs. 36%.
Cheon J. et al. [33].Single-arm, phase 2 trialRegorafenib after progression on first-line atezolizumab–bevacizumabmPFS 3.5 months (95% CI 3.0–3.9); mOS 10.5 months (95% CI 7.1–13.8); 6-month OS rate 65.0%; ORR 10.0%; DCR 82.5%.
Chan S.L. et al. [32]Phase 2, multicenter, single-arm trialCabozantinib following immune checkpoint inhibitor therapy in HCCIn second-line setting (n = 27), mPFS 4.3 months (95% CI 3.3–6.7); mOS 14.3 months (95% CI 8.9-NR).
RESORCE Trial [34]Randomized, double-blind, phase 3 trialPatients with HCC progressing on sorafenib: regorafenib vs. placeboRegorafenib improved OS (HR 0.63; 95% CI 0.50–0.79; p < 0.0001); mOS 10.6 vs. 7.8 months.
OS—overall survival, PFS—progression-free survival, DCR—disease control rate, ORR—overall response rate, HCC—hepatocellular carcinoma, TKI—tyrosine kinase inhibitor, AE—adverse events, ICI—immune checkpoint inhibitor, HR—hazard ratio, mOS—median OS, mPFS—median PFS.

3.4. ICI Rechallenge as Second-Line Therapy in Metastatic HCC

Resistance to initial ICI therapy in HCC may arise through adaptive immune mechanisms and changes in the tumor microenvironment [35,36,37]. Combination approaches and dual blockade with or without anti-VEGF can help overcome resistance by enhancing T cell activation and modulating the tumor microenvironment toward a pro-inflammatory state. This theoretically can resensitize the tumors to PD-L1 or CTLA4 blockade, which is the main biological rationale for the synergy observed with atezolizumab plus bevacizumab and post-ICI combination strategies [37].
Several studies have shown that response to nivolumab plus ipilimumab after prior anti-PD-1/PD-L1 therapy failure is variable and ranges approximately between 10 and 20% in melanoma, NSCLC, and renal cell carcinoma, among others [38,39,40]. A systematic review and meta-analysis of 60 studies showed that ICI rechallenge after prior discontinuation yielded an ORR of 21.6% and a disease control rate (DCR) of 55.8%, with grade ≥ 3 immune-related adverse events (irAEs) occurring in 16.7% of patients, with efficacy being highest in renal cell carcinoma (ORR 30.9%), followed by melanoma (24.3%) and NSCLC (10.1%) [41]. Rechallenge with combination ICIs targeting different pathways achieved better outcomes (ORR 22.5%, DCR 38%) than single-agent reuse, indicating that ICI retreatment can provide meaningful benefit with manageable toxicity in advanced solid tumors progressing after prior immunotherapy [41]. However, evidence for ICI retrial or rechallenge in hepatocellular carcinoma (HCC) remains limited compared to the more extensively studied TKI-based second-line approaches, highlighting a key gap in post-ICI treatment data for HCC and requires careful selection before consideration.
In a retrospective study by Lai et al. of HCC patients retreated with durvalumab after prior anti-PD-1 therapy (nivolumab or pembrolizumab), the overall response rate (ORR) was 13.8%, with higher responses among those who had previously responded to PD-1 inhibitors (31.3% vs. 8.7%, p—0.04) and among patients developing irAEs during durvalumab (35.3% vs. 6.7%, p—0.01). The median PFS was 5.4 months, and median OS was 9.6 months, extending to 33.9 months for prior responders. On multivariate analysis, response to prior anti-PD-1 therapy (HR 0.31) was the sole protective factor for survival, with skin and hepatic toxicities as the most common irAEs [42]. A case of massive HCC with portal vein tumor thrombus was reported, which showed a complete response to atezolizumab plus bevacizumab after progression on pembrolizumab plus lenvatinib, suggesting that anti-PD-L1 therapy can retain efficacy after anti-PD-1 resistance. PD-L1 blockade inhibits PD-L1 interaction with both PD-1 and B7.1 (CD80), enhancing T cell costimulation and antigen presentation, mechanisms not triggered by PD-1 antibodies with concurrent bevacizumab further reversing VEGF-mediated immunosuppression by normalizing vasculature, reducing MDSCs and Tregs, and improving dendritic cell maturation, collectively restoring immune infiltration and overcoming prior ICI resistance [43].
Roessler et al. conducted a retrospective study of HCC patients previously treated with atezolizumab plus bevacizumab or other ICI-based combinations. Among those, 10 patients received subsequent therapy with ipilimumab and nivolumab with an ORR of 30%, DCR of 40%, median PFS of 2.9 months, and OS of 7.4 months, indicating that dual ICI therapy can be effective and tolerable even after prior immunotherapy [44]. Wong et al. reviewed 25 patients with advanced HCC who progressed after prior ICI therapy, with ipilimumab plus nivolumab/pembrolizumab showing an ORR of 16% (3 complete responses) with a median DOR of 11.5 months, time to disease progression (TTP) of 2.96 months, and OS of 10.9 months. One-, two-, and three-year survival rates were 42.4%, 32.3%, and 21.6%, respectively. Responses occurred only in Child–Pugh A, ALBI 1–2 patients. Therapy-related adverse events occurred in 52% (grade ≥ 3 in 12%), indicating durable efficacy with acceptable toxicity; however, ICI-based retreatment should be approached cautiously and reserved for patients with adequate liver function, as 12% experienced grade ≥ 3 treatment-related adverse events, and poorer outcomes were observed in those with higher Child–Pugh class or ALBI grade [45]. In a multi-site Mayo Clinic study of HCC patients treated with first-line atezolizumab/bevacizumab between 2018 and 2022, 107 of 342 patients (31.3%) went on to receive second-line systemic therapy. Median overall survival (OS) from initiation of second-line treatment was 11.1 months overall, with no significant difference between anti-VEGF therapy (median OS 10.7 months, 95% CI 7.2–12.8) and immune checkpoint inhibitors (median OS 15.7 months, 95% CI 6.8-NE; p = 0.50). Median time to treatment discontinuation was similarly short for anti-VEGF inhibitors (2.4 months, 95% CI 1.7–3.3) and ICIs (2.6 months, 95% CI 1.5–5.1; p = 0.87), and Child–Pugh score was significantly associated with survival in a multivariate analysis [46].
NCT04430452 is an ongoing phase II open-label trial in 30 patients with advanced HCC, and a Child–Pugh score A and B less than 9, progressing after prior ICIs (excluding durvalumab), evaluating 5-day hypofractionated radiotherapy followed by durvalumab alone or with tremelimumab every 4 weeks for up to 2 years, with the objective response rate as the primary endpoint.
It is important to highlight that ICI rechallenge in metastatic or advanced HCC remains nonstandard with limited evidence. This should be explored in the context of clinical trials or highly selected patients.

3.5. TKIs Plus ICI Rechallenge vs. TKI Alone as Second-Line Therapy in Metastatic HCC

A multicenter retrospective study (Yu, J. et al.) comparing regorafenib plus ICI vs. regorafenib alone as second-line treatment after ICI failure showed significantly improved OS [19.0 vs. 11.0 months, hazard ratio (HR) = 0.426, 95% confidence interval (CI): 0.235–0.772, p—0.005] and PFS (4.0 vs. 3.0 months, HR—0.539, 95% CI: 0.337–0.863, p—0.010) compared to the regorafenib group [47], with a median PFS of 5.09 months in another similar study (Zhao, J et al.) [48]. In a retrospective study (Lai, K. C. et al.), cabozantinib plus ICI showed better PFS vs. cabozantinib alone (6.7 vs. 3.2 months; p—0.04) with a trend toward longer OS with exploratory analyses suggesting AXL expression may predict benefit [49].
A phase III trial (IMbrave251)/NCT04770896 is currently evaluating ICI in combination with TKI/VEGF inhibitors comparing atezolizumab combined with lenvatinib or sorafenib versus lenvatinib or sorafenib alone in patients with unresectable or metastatic HCC who have progressed on prior atezolizumab plus bevacizumab treatment, but side effects like active varices, uncontrolled portal hypertension, recent gastrointestinal bleeding, or uncontrolled hypertension would be a limiting factor.
In a multicenter phase 1b/2 study (Hsu, C. et al.), GT90001 (anti-ALK-1 monoclonal antibody) plus nivolumab achieved a median PFS of 2.81 months (95% CI, 1.71–9.33) for first-line therapy in metastatic HCC without prior ICI exposure, and a phase II trial (NCT05178043) to approve its use in second-line therapy is going on [50].
Regarding third-line therapy post-sorafenib, multiple RCTs like the RESORCE and REACH2 trials show survival benefit with ramucirumab (AFP ≥ 400 ng/mL: 8.5 vs. 7.3 months; p—0.0199), regorafenib (10.6 vs. 8.0 months, p < 0.001), and cabozantinib (10.2 vs. 8.0 months, p—0.005), with generally manageable TKI toxicities (hand–foot skin reaction, fatigue, hypertension, proteinuria) [30,34,51]. Ramucirumab is currently FDA-approved for patients with advanced HCC with preserved liver function and AFP > 400 ng/mL who have had disease progression on sorafenib.

3.6. Oligoprogressive Disease in HCC

In metastatic hepatocellular carcinoma (HCC), oligoprogressive disease (OPD) refers to limited progression, typically involving ≤3–5 lesions in ≤2 organs while the remaining disease remains controlled on ongoing systemic therapy such as immune checkpoint inhibitors (ICIs) or tyrosine kinase inhibitors (TKIs). This pattern reflects focal or clonal resistance rather than global treatment failure and provides an opportunity to maintain effective systemic therapy while addressing resistant lesions with local treatments. Modalities such as stereotactic body radiotherapy (SBRT), radiofrequency or microwave ablation (RFA/MWA), or transarterial radioembolization (TARE) can achieve local control, delay systemic progression, and potentially prolong overall survival.

3.7. Locoregional Therapy

Transarterial chemoembolization (TACE) delivers chemotherapeutic agents such as doxorubicin or cisplatin into the hepatic artery supplying the tumor, followed by embolization to block blood flow, inducing ischemic necrosis and high local drug concentration while sparing normal liver tissue. Transarterial radioembolization (TARE or Y-90) involves the intra-arterial infusion of yttrium-90-labeled microspheres that deliver localized beta radiation to tumor tissue, inducing direct cytotoxicity, endothelial damage, and immunogenic cell death while sparing healthy parenchyma. Radiofrequency ablation (RFA) and microwave ablation (MWA) employ high-frequency electrical currents or electromagnetic waves to generate thermal coagulative necrosis, most effective for tumors smaller than 3 cm, leading to localized tumor destruction and the release of tumor-associated antigens. Hepatic arterial infusion chemotherapy (HAIC) administers concentrated chemotherapeutic agents such as FOLFOX or cisplatin/5-FU directly into the hepatic artery, achieving potent regional cytotoxicity with minimal systemic toxicity and particular efficacy in cases with macrovascular invasion like portal vein thrombosis. Stereotactic body radiotherapy (SBRT) delivers highly focused, high-dose radiation to tumor sites, causing double-strand DNA breaks and immunogenic tumor cell death, which upregulates PD-L1 expression and enhances antigen presentation, thereby facilitating immune-mediated tumor clearance [8]. The resulting hypoxia from these procedures triggers VEGF release and angiogenesis, which can be counteracted by TKIs like sorafenib or lenvatinib to enhance tumor control. TACE-induced necrosis also releases tumor antigens and damage-associated molecular patterns, promoting dendritic cell activation and T cell priming, upregulates PD-L1 and MHC-I, augmenting response to PD-1/PD-L1 inhibitors; when combined with ICIs, this immunogenic effect boosts antitumor immunity and creates an “in situ vaccine” effect that enhances systemic response [52].
Talbot et al. found that new vascular invasion was a common progression pattern post-ICI, associated with shorter OS (HR 2.15; p—0.0007, median OS 0.4 months), suggesting a role for SBRT in controlling vascular invasion [22].

LRT Plus TKI/ICI vs. LRT Alone

In the phase 3 TACTICS trial, TACE plus sorafenib achieved a median OS of 36.2 vs. 30.8 months with TACE alone (HR 0.86, p—0.40) and significantly improved PFS (22.8 vs. 13.5 months; HR 0.66, p—0.02). Although OS benefit was not statistically significant, the combination provided clinically meaningful survival prolongation, supporting TACE plus sorafenib as an effective option for unresectable HCC [52]. In a multicenter, randomized, phase III trial, patients with treatment-naive or recurrent advanced HCC were assigned to lenvatinib plus on-demand TACE (LEN-TACE) or lenvatinib monotherapy. At a median follow-up of 17 months, LEN-TACE significantly improved overall survival (17.8 vs. 11.5 months), progression-free survival (10.6 vs. 6.4 months), and higher objective response rate (54.1% vs. 25.0%) in the LEN-TACE group, and multivariable analysis identified portal vein tumor thrombus and treatment allocation as independent prognostic factors [53]. Clinically, small phase II and real-world studies (like NCT04224636/DEMAND phase II trial, EMERALD-1, CheckMate-74W/NCT04340193, LEAP-012) show that TACE plus ICI (±anti-VEGF) achieves higher ORR (40–60%), longer PFS (10 to 12 months vs. 6 to 8 months), and improved local control, without major increases in toxicity compared with TACE alone. These findings suggest that TACE combined with ICIs may convert locoregional therapy into a systemic immunomodulatory approach, potentially redefining treatment for intermediate or unresectable HCC pending the results of ongoing phase III trials, as mentioned in Table 2 [54,55,56].
Duffy et al. reported in a cohort of 32 patients treated with tremelimumab plus LRT (TACE, RFA, or cryoablation) a partial response rate of 26.3%, 6- and 12-month PFS rates of 57.1% and 33.1%, and a median OS of 12.3 months, indicating enhanced efficacy and immune activation with combined approaches [57]. In a phase II single-arm study (Tai, D. et al.), 40 patients with advanced hepatocellular carcinoma and Child–Pugh A liver function received Y90 radioembolization followed by nivolumab 240 mg every two weeks starting 21 days after Y90. Of the 36 patients who completed both treatments, the objective response rate was 30.6% (95% CI 16.4–48.1), including one complete and ten partial responses. The combination was well tolerated and demonstrated promising antitumor activity, though the response rate was lower than the target estimate, concluding that Y90 followed by nivolumab shows encouraging efficacy in advanced HCC, warranting further evaluation in BCLC stage B patients ineligible or refractory to TACE and in stage C disease without extrahepatic spread [58]. In a meta-analysis by Ding et al. including 1774 patients across 19 studies, combining cellular immunotherapy with LRT (mainly TACE) significantly improved the disease control rate (OR 5.91, p—0.007), 1-year PFS (OR 3.56, p < 0.00001), and 24-month OS (OR 3.52, p < 0.0001) compared to LRT alone, as mentioned in Table 2 [59].
In the phase III randomized trial by Dawson et al., patients receiving SBRT followed by sorafenib had significantly improved outcomes compared with sorafenib alone, with a median overall survival of 15.8 vs. 12.3 months (HR 0.72; 95% CI 0.52–0.99; p = 0.042) and a median progression-free survival of 9.2 vs. 5.5 months (HR 0.55; 95% CI 0.40–0.75; p = 0.0001), demonstrating that adding SBRT to systemic therapy enhances survival and disease control in advanced HCC, as mentioned in Table 2 [60].
The phase 2 NASIR-HCC trial included 42 patients with unresectable HCC (BCLC-B2 or unilobar portal vein invasion) who received SIRT followed by nivolumab. Over 22.2 months of follow-up, treatment-related grade 3/4 adverse events occurred in eight patients (5 serious), indicating acceptable safety. The objective response rate was 41.5%, with four patients downstaged to surgery. Median time to progression was 8.8 months and overall survival 20.9 months, showing that SIRT plus nivolumab provides manageable toxicity and meaningful antitumor activity in intermediate to locally advanced HCC, as mentioned in Table 2 [61].
In a single-group phase II multicenter trial, 50 patients with advanced HCC and macrovascular invasion received concurrent nivolumab and external beam radiotherapy (EBRT), followed by maintenance nivolumab. Median progression-free survival was 5.6 months, overall survival 15.2 months, and time to progression 5.6 months, with an ORR of 36% and disease control rate 74%, and a median response duration of 9.9 months. Treatment-related adverse events occurred in 80% of patients, with grade 3/4 events in 12%, indicating acceptable safety. Overall, concurrent nivolumab plus EBRT demonstrated promising efficacy and manageable toxicity in this high-risk HCC population [62].
Kumar, R et al. conducted a retrospective study of advanced HCC with portal vein tumor thrombosis (PVTT); stereotactic body radiotherapy (SBRT) achieved 1-year local control, progression-free survival, and overall survival rates of 95%, 53.4%, and 60%, respectively, with minimal grade III toxicity. Tumors larger than 350 cc had significantly poorer outcomes, with a median OS and PFS of 4 and 2 months (p—0.01 and 0.003), and the median time to progression was 2 months, indicating that SBRT provides excellent local control and manageable toxicity in advanced HCC with PVTT, though early systemic relapse highlights the need for multimodal therapy integration [63].
Table 2. Locoregional therapy in metastatic HCC.
Study/TrialStudy DesignStudy Population/InterventionKey Results
TACTICS TrialRandomized, prospective clinical trialUnresectable HCC: TACE plus sorafenib vs. TACE alonemOS 36.2 vs. 30.8 months (HR 0.86; 95% CI 0.61–1.22; p = 0.40); updated PFS significantly improved with TACE plus sorafenib (22.8 vs. 13.5 months; HR 0.66; 95% CI 0.47–0.94; p = 0.02).
LAUNCH TrialRandomized clinical trialAdvanced HCC: lenvatinib plus TACE vs. lenvatinib alonemOS 17.8 vs. 11.5 months (HR 0.45; p < 0.001); PFS 10.6 vs. 6.4 months (HR 0.43; p < 0.001); higher ORR with LEN-TACE (54.1% vs. 25.0%; p < 0.001).
DEMAND Trial (NCT04224636)Multicenter, randomized phase II studyIntermediate-stage HCC: atezolizumab–bevacizumab before or with TACEOutcomes pending; primary endpoint 24-month survival rate; secondary endpoints include ORR, PFS, safety, and quality of life.
EMERALD-1 (NCT03778957)Multiregional, randomized, double-blind, placebo-controlled phase III trialIntermediate-stage HCC: TACE plus durvalumab ± bevacizumab vs. placebomPFS 15.0 months with durvalumab plus bevacizumab vs. 8.2 months with placebo (HR 0.77; p = 0.032); durvalumab alone did not significantly improve PFS vs. placebo (HR 0.94; p = 0.64).
CheckMate 74W (NCT04340193)Global, randomized, double-blind phase III trialIntermediate-stage HCC: nivolumab plus ipilimumab plus TACE vs. controlsOngoing; primary endpoint time to TACE progression; secondary endpoints include OS, PFS, and event-free survival.
LEAP-012Prospective, randomized, double-blind phase III trialIntermediate-stage HCC: lenvatinib plus pembrolizumab plus TACE vs. placebo plus TACEOngoing; dual primary endpoints OS and PFS; secondary endpoints include ORR, DCR, duration of response, and time to progression.
Duffy et al. [57]. (NCT01853618)Phase I/II clinical studyRefractory HCC: tremelimumab combined with ablation6- and 12-month tumor PFS rates 57.1% and 33.1%; median time to progression 7.4 months; mOS 12.3 months (95% CI 9.3–15.4).
Tai D. et al. [58].Single-arm, single-center phase II trialAdvanced HCC: Y90 radioembolization followed by nivolumabORR 30.6% (95% CI 16.4–48.1); CR 3%, PR 28%.
Ding et al. [59].Meta-analysis (19 studies, n = 1774)Cellular immunotherapy plus LRT (mainly TACE) vs. LRT aloneImproved DCR (OR 5.91; p = 0.007), 1-year PFS (OR 3.56; p < 0.00001), and 24-month OS (OR 3.52; p < 0.0001).
Dawson et al. [60].Randomized phase III trialAdvanced HCC: SBRT plus sorafenib vs. sorafenib alonemOS 15.8 vs. 12.3 months (HR 0.72; p = 0.042); mPFS 9.2 vs. 5.5 months (HR 0.55; p = 0.0001).
NASIR-HCCPhase II trialUnresectable HCC (BCLC-B2 or unilobar PV invasion): SIRT followed by nivolumabORR 41.5%; four patients downstaged to surgery; median TTP 8.8 months; mOS 20.9 months.
Kim B. et al. [62].Phase II multicenter single-arm trialHCC with macrovascular invasion: concurrent nivolumab and EBRT followed by nivolumabmPFS 5.6 months; mOS 15.2 months; ORR 36%; DCR 74%.
OS—overall survival, PFS—progression-free survival, DCR—disease control rate, ORR—overall response rate, mOS—median OS, mPFS—median PFS, HCC—hepatocellular carcinoma, LRT—locoregional therapy, TACE—transarterial chemoembolization, SBRT—stereotactic body radiation therapy, SIRT—selective internal radiation therapy, EBRT—external beam radiation therapy, TTP—time to progression.

3.8. Cellular Therapy/CAR-T

Chimeric antigen receptor T cell therapy (CAR-T) is an innovative and emerging therapy in different cancers, including HCC [64]. Unlike hematological malignancies where CAR-T is the standard of care for many hematological malignancies, CAR-T development in solid tumors including HCC remains investigational and faces challenges, in particular, due to the tumor heterogeneity, on-target off-tumor toxicity and the immune microenvironment [64]. Studies have evaluated multiple target antigens for CAR-T in HCC and among those, Glypican-3 (GPC3) represents the most promising target aiming at the high level of expression in HCC [65]. Zhang et al. presented at the American Society of Clinical Oncology (ASCO) 2024 preliminary results of the first-in-human phase I study using a GPC3-directed CAR-T therapy, C-CAR301 [66]. The trial demonstrated a manageable safety profile in these heavily pretreated patients with HCC with no dose-limiting toxicities and predominantly low-grade cytokine release syndrome (CRS). Preliminary efficacy indicated tumor reduction in 90.9% of patients, with a DCR of 90.9% and ORR of 50%, supporting further clinical development. Currently, there are several clinical trials evaluating this approach, as mentioned in Table 3 [67,68,69]. The available CAR-T data are limited by short follow-up, absence of mature survival endpoints, small cohort sizes, and the strictly early-phase investigational status of these trials and therefore should not be interpreted as practice-defining.

3.9. LRT as Second-Line Therapy

In this retrospective study of advanced HCC, HAIC (hepatic arterial infusion chemotherapy) after atezolizumab–bevacizumab failure achieved better outcomes than first-line HAIC, with a median OS of 12.4 vs. 6.8 months (p—0.073), PFS of 8.2 vs. 3.1 months (p—0.018), and ORR of 35.3% vs. 18.1% (p—0.031). Multivariate analysis confirmed HAIC post-atezolizumab plus bevacizumab as an independent predictor of improved OS and PFS, supporting its potential as an effective second-line therapy pending validation in larger trials [70]. A multicenter, open-label phase III trial is going on to evaluate HAIC plus regorafenib versus regorafenib alone in advanced HCC patients intolerant of or progressing after first-line therapy, with treatment given in 4-week cycles and overall survival as the primary endpoint [71].
Sindhu et al. analyzed 30 patients with solid tumors, including 16 patients with HCC and urothelial carcinoma among others, who received SBRT (stereotactic body radiation therapy) after oligoprogression during ICI therapy. The median time to oligoprogression was 11.1 months, and patients received a median RT dose of 46.5 Gy in five fractions. Post-RT, the median progression-free survival (PFS) was 7.1 months, with 26 patients continuing ICIs and 15 showing limited subsequent progression amenable to additional RT. Overall survival at 6, 12, and 24 months was 100%, 96.3%, and 82.8%, respectively. These findings suggest that targeted RT during oligoprogression can prolong disease control and sustain ICI efficacy, achieving excellent overall survival outcomes [72].

4. Summary and Limitations of Current Evidence

To summarize, as mentioned in Figure 1, in the second-line setting for unresectable/advanced HCC, management is guided by prior treatment exposure, hepatic reserve (Child–Pugh), ECOG performance status, and overall patient fitness. For fit patients with preserved liver functions, current evidence supports TKI monotherapy with options including lenvatinib, sorafenib, and cabozantinib. Regorafenib can be considered after prior progression to sorafenib. Enrollment in a clinical trial should be considered whenever available. Notably, evidence supporting rechallenge with ICIs remains limited, and this approach is not considered standard outside of clinical trials or in highly selected patients. In patients with oligoprogressive disease on an otherwise effective systemic therapy, locoregional therapy (LRT) should be considered while continuing with the current systemic agent rather than switching lines.
The majority of included studies are limited by small sample sizes, retrospective design, and inherent selection bias, which restrict the generalizability of the reported outcomes. Given the underlying cirrhosis in most HCC patients, efficacy outcomes must be interpreted alongside rates of hepatic decompensation, liver-related toxicity, and treatment-associated mortality, which remain underreported across the included studies. In the absence of phase III randomized controlled trial data, the therapeutic strategies discussed in this review should be considered hypothesis-generating and practice-informing rather than evidence-based recommendations, and no definitive therapeutic efficacy recommendations can be established at this time, emphasizing the need for well-designed larger prospective studies or RCTs at this time.

5. Conclusions

Second-line treatment of advanced HCC after ICI failure remains a critical research gap. TKIs, particularly lenvatinib, remain the most reliable empirical choice, supported by retrospective studies and biologic mechanism of action. Rechallenge with immunotherapy after prior exposure to ICIs is not supported by high-level evidence and should be considered in the context of clinical trials or highly selected patient populations. Locoregional therapies still play an important role, especially in oligoprogressive disease, and may synergize with systemic strategies. In the absence of randomized data, treatment selection must be individualized, guided by liver function, ECOG status, prior response to ICI, comorbidities, and disease distribution. Cellular therapies with CAR-T cells remain investigational but early clinical signals, particularly with GPC3-targeted CAR-T, are promising, supporting continued development and optimization to define their role in HCC.
TKIs: Lenvatinib, sorafenib, cabozantinib, regorafenib, rivoceranib.
ICIs: Atezolizumab, durvalumab, nivolumab, pembrolizumab, camrelizumab, ipilimumab, tremelimumab.

Author Contributions

Original draft writing—S.S.M.V. A.A.—visual abstract, editing and revisions. U.M.—manuscript editing and revisions. N.O.—manuscript editing and revisions. O.M.M.—supervision, manuscript final edits. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

Not applicable.

Informed Consent Statement

Not applicable.

Data Availability Statement

No new data were created or analyzed in this study. Data sharing is not applicable to this article.

Acknowledgments

During the preparation of this manuscript/study, the authors used Claude Sonnet model 5 for the purposes of creation of the visual abstract. Figure 1 was created using Biorender. Com. The authors have reviewed and edited the output and take full responsibility for the content of this publication.

Conflicts of Interest

The authors declare no conflicts of interest.

Abbreviations

Additional abbreviations—OS—overall survival, PFS—progression-free survival, DCR—disease control rate, ORR—overall response rate, AE—adverse events, TACE—transarterial chemoembolization, SBRT—stereotactic body radiation therapy, SIRT—selective internal radiation therapy, EBRT—external beam radiation therapy, TTP—time to progression, HAIC—hepatic arterial infusion chemotherapy, CAR-T—chimeric antigen receptor T cell, GPC—Glypican, CCL-19—C-C motif chemokine ligand 19, HBV—hepatitis B virus, HCV—hepatitis C virus, MASLD—metabolic dysfunction-associated steatotic liver disease, BCLC—Barcelona Clinic Liver Cancer staging system.

References

  1. Sung, H.; Ferlay, J.; Siegel, R.L.; Laversanne, M.; Soerjomataram, I.; Jemal, A.; Bray, F. Global Cancer Statistics 2020: GLOBOCAN Estimates of Incidence and Mortality Worldwide for 36 Cancers in 185 Countries. CA Cancer J. Clin. 2021, 71, 209–249. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. McGlynn, K.A.; Petrick, J.L.; El-Serag, H.B. Epidemiology of Hepatocellular Carcinoma. Hepatology 2021, 73, 4–13. [Google Scholar] [CrossRef] [Scilit]
  3. El-Serag, H.B.; Kanwal, F. Epidemiology of hepatocellular carcinoma in the United States: Where are we? Where do we go? Hepatology 2014, 60, 1767–1775. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Xu, J. Trends in Liver Cancer Mortality Among Adults Aged 25 and Over in the United States, 2000–2016. NCHS Data Brief 2018, 314, 1–8. [Google Scholar]
  5. Villanueva, A. Hepatocellular Carcinoma. N. Engl. J. Med. 2019, 380, 1450–1462. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Su, G.L.; Altayar, O.; O’Shea, R.; Shah, R.; Estfan, B.; Wenzell, C.; Sultan, S.; Falck-Ytter, Y. AGA Clinical Practice Guideline on Systemic Therapy for Hepatocellular Carcinoma. Gastroenterology 2022, 162, 920–934. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Kudo, M. Systemic Therapy Combined with Locoregional Therapy in Intermediate-stage Hepatocellular Carcinoma. Interv. Radiol. 2025, 10, e20230035. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Wang, K.; Wang, C.; Jiang, H.; Zhang, Y.; Lin, W.; Mo, J.; Jin, C. Combination of Ablation and Immunotherapy for Hepatocellular Carcinoma: Where We Are and Where to Go. Front. Immunol. 2021, 12, 792781. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Melero, I.; Yau, T.; Kang, Y.K.; Kim, T.-Y.; Santoro, A.; Sangro, B.; Kudo, M.; Hou, M.-M.; Matilla, A.; Tovoli, F.; et al. Nivolumab plus ipilimumab combination therapy in patients with advanced hepatocellular carcinoma previously treated with sorafenib: 5-year results from CheckMate 040. Ann. Oncol. 2024, 35, 537–548. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Cheng, A.L.; Qin, S.; Ikeda, M.; Galle, P.R.; Ducreux, M.; Kim, T.-Y.; Lim, H.Y.; Kudo, M.; Breder, V.; Merle, P.; et al. Updated efficacy and safety data from IMbrave150: Atezolizumab plus bevacizumab vs. sorafenib for unresectable hepatocellular carcinoma. J. Hepatol. 2022, 76, 862–873. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Sangro, B.; Chan, S.L.; Kelley, R.K.; Lau, G.; Kudo, M.; Sukeepaisarnjaroen, W.; Yarchoan, M.; De Toni, E.N.; Furuse, J.; Kang, Y.K.; et al. Four-year overall survival update from the phase III HIMALAYA study of tremelimumab plus durvalumab in unresectable hepatocellular carcinoma. Ann. Oncol. 2024, 35, 448–457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Qin, S.; Chan, S.L.; Gu, S.; Bai, Y.; Ren, Z.; Lin, X.; Chen, Z.; Jia, W.; Jin, Y.; Guo, Y.; et al. Camrelizumab plus rivoceranib versus sorafenib as first-line therapy for unresectable hepatocellular carcinoma (CARES-310): A randomised, open-label, international phase 3 study. Lancet 2023, 402, 1133–1146. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Yau, T.; Kaseb, A.; Cheng, A.L.; Qin, S.; Zhu, A.X.; Chan, S.L.; Melkadze, T.; Sukeepaisarnjaroen, W.; Breder, V.; Verset, G.; et al. Cabozantinib plus atezolizumab versus sorafenib for advanced hepatocellular carcinoma (COSMIC-312): Final results of a randomised phase 3 study. Lancet Gastroenterol. Hepatol. 2024, 9, 310–322. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Llovet, J.M.; Kudo, M.; Merle, P.; Meyer, T.; Qin, S.; Ikeda, M.; Xu, R.; Edeline, J.; Ryoo, B.-Y.; Ren, Z.; et al. Lenvatinib plus pembrolizumab versus lenvatinib plus placebo for advanced hepatocellular carcinoma (LEAP-002): A randomised, double-blind, phase 3 trial. Lancet Oncol. 2023, 24, 1399–1410. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Yamashita, T.; Kudo, M.; Ikeda, K.; Izumi, N.; Tateishi, R.; Ikeda, M.; Aikata, H.; Kawaguchi, Y.; Wada, Y.; Numata, K.; et al. REFLECT-a phase 3 trial comparing efficacy and safety of lenvatinib to sorafenib for the treatment of unresectable hepatocellular carcinoma: An analysis of Japanese subset. J. Gastroenterol. 2020, 55, 113–122. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Qin, S.; Kudo, M.; Meyer, T.; Bai, Y.; Guo, Y.; Meng, Z.; Satoh, T.; Marino, D.; Assenat, E.; Li, S.; et al. Tislelizumab vs Sorafenib as First-Line Treatment for Unresectable Hepatocellular Carcinoma: A Phase 3 Randomized Clinical Trial. JAMA Oncol. 2023, 9, 1651–1659. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Kim, C.G.; Kim, C.; Yoon, S.E.; Kim, K.H.; Choi, S.J.; Kang, B.; Kim, H.R.; Park, S.H.; Shin, E.C.; Kim, Y.Y.; et al. Hyperprogressive disease during PD-1 blockade in patients with advanced hepatocellular carcinoma. J. Hepatol. 2021, 74, 350–359. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Chan, S.L. Hyperprogression in hepatocellular carcinoma: Illusion or reality? J. Hepatol. 2021, 74, 269–271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Denis, M.; Duruisseaux, M.; Brevet, M.; Dumontet, C. How Can Immune Checkpoint Inhibitors Cause Hyperprogression in Solid Tumors? Front. Immunol. 2020, 11, 492. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Zhang, L.; Wu, L.; Chen, Q.; Zhang, B.; Liu, J.; Liu, S.; Mo, X.; Li, M.; Chen, Z.; Chen, L.; et al. Predicting hyperprogressive disease in patients with advanced hepatocellular carcinoma treated with anti-programmed cell death 1 therapy. eClinicalMedicine 2021, 31, 100673. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Wu, M.; Fulgenzi, C.A.M.; D’Alessio, A.; Cortellini, A.; Celsa, C.; Manfredi, G.F.; Stefanini, B.; Wu, Y.L.; Huang, Y.-H.; Saeed, A.; et al. Second-line treatment patterns and outcomes in advanced HCC after progression on atezolizumab/bevacizumab. JHEP Rep. 2025, 7, 101232. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Talbot, T.; D’Alessio, A.; Pinter, M.; Balcar, L.; Scheiner, B.; Marron, T.U.; Jun, T.; Dharmapuri, S.; Ang, C.; Saeed, A.; et al. Progression patterns and therapeutic sequencing following immune checkpoint inhibition for hepatocellular carcinoma: An international observational study. Liver Int. 2023, 43, 695–707. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. da Fonseca, L.G.; Reig, M.; Bruix, J. Tyrosine Kinase Inhibitors and Hepatocellular Carcinoma. Clin. Liver Dis. 2020, 24, 719–737. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Xie, Y.; Wu, H.; He, Y.; Liu, L.; Huang, I.B.; Zhou, L.; Lin, C.-Y.; Leung, R.W.-H.; Loh, J.-J.; Lee, T.K.-W.; et al. Targeting AXL induces tumor-intrinsic immunogenic response in tyrosine kinase inhibitor-resistant liver cancer. Cell Death Dis. 2024, 15, 110. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Asaoka, Y.; Tanaka, A. Clinical implications of WNT/β-catenin signaling for hepatocellular carcinoma. Glob. Health Med. 2020, 2, 269–272. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Yi, C.; Chen, L.; Lin, Z.; Liu, L.; Shao, W.; Zhang, R.; Lin, J.; Zhang, J.; Zhu, W.; Jia, H.; et al. Lenvatinib Targets FGF Receptor 4 to Enhance Antitumor Immune Response of Anti-Programmed Cell Death-1 in HCC. Hepatology 2021, 74, 2544–2560. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Kim, H.D.; Sym, S.J.; Chon, H.J.; Kim, M.; Kang, J.H.; Ryoo, B.-Y.; Lee, C.-K.; Hong, J.; Ryu, H.; Bae, W.K.; et al. Multicenter single-arm phase II trial of lenvatinib in patients with advanced hepatocellular carcinoma after progression on first-line atezolizumab plus bevacizumab. J. Hepatol. 2025, 84, 308–315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Chon, Y.E.; Kim, D.Y.; Kim, M.N.; Kim, B.K.; Kim, S.U.; Park, J.Y.; Ahn, S.H.; Ha, Y.; Lee, J.H.; Lee, K.S.; et al. Sorafenib vs. Lenvatinib in advanced hepatocellular carcinoma after atezolizumab/bevacizumab failure: A real-world study. Clin. Mol. Hepatol. 2024, 30, 345–359. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Cabibbo, G.; Reig, M.; Celsa, C.; Torres, F.; Battaglia, S.; Enea, M.; Rizzo, G.E.M.; Petta, S.; Calvaruso, V.; Di Marco, V.; et al. First-Line Immune Checkpoint Inhibitor-Based Sequential Therapies for Advanced Hepatocellular Carcinoma: Rationale for Future Trials. Liver Cancer 2022, 11, 75–84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Abou-Alfa, G.K.; Meyer, T.; Cheng, A.L.; El-Khoueiry, A.B.; Rimassa, L.; Ryoo, B.Y.; Cicin, I.; Merle, P.; Chen, Y.; Park, J.W.; et al. Cabozantinib in Patients with Advanced and Progressing Hepatocellular Carcinoma. N. Engl. J. Med. 2018, 379, 54–63. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Storandt, M.H.; Gile, J.J.; Palmer, M.E.; Zemla, T.J.; Ahn, D.H.; Bekaii-Saab, T.S.; Jin, Z.; Tran, N.H.; Mahipal, A. Cabozantinib Following Immunotherapy in Patients with Advanced Hepatocellular Carcinoma. Cancers 2022, 14, 5173. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Chan, S.L.; Ryoo, B.Y.; Mo, F.; Chan, L.L.; Cheon, J.; Li, L.; Wong, K.H.; Yim, N.; Kim, H.; Yoo, C. Multicentre phase II trial of cabozantinib in patients with hepatocellular carcinoma after immune checkpoint inhibitor treatment. J. Hepatol. 2024, 81, 258–264. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Cheon, J.; Ryoo, B.Y.; Chon, H.J.; Kim, H.-D.; Ryu, M.-H.; Kim, K.-P.; Kang, B.; Finn, R.S.; Chan, S.L.; Yoo, C. Multicenter Phase 2 Trial of Second-Line Regorafenib in Patients with Unresectable Hepatocellular Carcinoma after Progression on Atezolizumab plus Bevacizumab. Liver Cancer 2025, 14, 446–455. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Bruix, J.; Qin, S.; Merle, P.; Granito, A.; Huang, Y.-H.; Bodoky, G.; Pracht, M.; Yokosuka, O.; Rosmorduc, O.; Breder, V.; et al. Regorafenib for patients with hepatocellular carcinoma who progressed on sorafenib treatment (RESORCE): A randomised, double-blind, placebo-controlled, phase 3 trial. Lancet 2017, 389, 56–66. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Brossart, P. The Role of Antigen Spreading in the Efficacy of Immunotherapies. Clin. Cancer Res. 2020, 26, 4442–4447. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Cai, L.; Li, Y.; Tan, J.; Xu, L.; Li, Y. Targeting LAG-3, TIM-3, and TIGIT for cancer immunotherapy. J. Hematol. Oncol. 2023, 16, 101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  37. Kudo, M. Scientific Rationale for Combination Immunotherapy of Hepatocellular Carcinoma with Anti-PD-1/PD-L1 and Anti-CTLA-4 Antibodies. Liver Cancer 2019, 8, 413–426. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Zimmer, L.; Apuri, S.; Eroglu, Z.; Kottschade, L.A.; Forschner, A.; Gutzmer, R.; Schlaak, M.; Heinzerling, L.; Krackhardt, A.M.; Loquai, C.; et al. Ipilimumab alone or in combination with nivolumab after progression on anti-PD-1 therapy in advanced melanoma. Eur. J. Cancer 2017, 75, 47–55. [Google Scholar] [CrossRef] [Scilit]
  39. Sternschuss, M.; Peled, N.; Allen, A.M.; Dudnik, E.; Rotem, O.; Kurman, N.; Gal, O.; Reches, H.; Zer, A. Can Ipilimumab restore immune response in advanced NSCLC after progression on anti-PD-1/PD-L1 agents? Thorac. Cancer 2020, 11, 2331–2334. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Gul, A.; Stewart, T.F.; Mantia, C.M.; Shah, N.J.; Gatof, E.S.; Long, Y.; Allman, K.D.; Ornstein, M.C.; Hammers, H.J.; McDermott, D.F.; et al. Salvage Ipilimumab and Nivolumab in Patients with Metastatic Renal Cell Carcinoma After Prior Immune Checkpoint Inhibitors. J. Clin. Oncol. 2020, 38, 3088–3094. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Cao, J.; Ding, X.; Ji, J.; Zhang, L.; Luo, C. Efficacy and safety of immune checkpoint inhibitors rechallenge in advanced solid tumors: A systematic review and meta-analysis. Front. Oncol. 2024, 14, 1475502. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  42. Lai, K.C.; Chen, Y.H.; Hung, Y.P.; Chiang, N.J.; Chen, M.; Chen, S.C. Efficacy and safety of durvalumab rechallenge in advanced hepatocellular carcinoma patient’s refractory to prior anti-PD-1 therapy. Hepatol. Int. 2024, 18, 1804–1814. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Liu, G.; Zhou, W.; Li, X.; Guo, L.; He, T.; Zhao, J.; Gong, L. Case Report: Complete Response of Primary Massive Hepatocellular Carcinoma to Anti-Programmed Death Ligand-1 Antibody Following Progression on Anti-Programmed Death-1 Antibody. Front. Immunol. 2021, 12, 712351. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Roessler, D.; Öcal, O.; Philipp, A.B.; Markwardt, D.; Munker, S.; Mayerle, J.; Jochheim, L.S.; Hammer, K.; Lange, C.M.; Geier, A.; et al. Ipilimumab and nivolumab in advanced hepatocellular carcinoma after failure of prior immune checkpoint inhibitor-based combination therapies: A multicenter retrospective study. J. Cancer Res. Clin. Oncol. 2023, 149, 3065–3073. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Wong, J.S.L.; Kwok, G.G.W.; Tang, V.; Li, B.C.W.; Leung, R.; Chiu, J.; Ma, K.W.; She, W.H.; Tsang, J.; Lo, C.M.; et al. Ipilimumab and nivolumab/pembrolizumab in advanced hepatocellular carcinoma refractory to prior immune checkpoint inhibitors. Immunother. Cancer 2021, 9, e001945. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Marell, P.; Kournoutas, I.; Gile, J.; Peersen, A.; Shah, P.; Babiker, H.; Kankeu, L.F.; Washburn, L.; Graham, R.; Truty, M.; et al. Second-line therapies in advanced hepatocellular carcinoma following first-line atezolizumab and bevacizumab: Multicenter single institution cohort experience. Oncologist 2025, 30, oyae342. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  47. Yu, J.; Bai, Y.; Cui, Z.; Ladekarl, M.; Cheng, K.-C.; Chan, K.S.; Yarmohammadi, H.; Mauriz, J.L.; Zhang, Y. Efficacy and safety of regorafenib as a first-line agent alone or in combination with an immune checkpoint inhibitor for advanced hepatocellular carcinoma: A retrospective cohort study. J. Gastrointest. Oncol. 2024, 15, 1072–1081. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  48. Zhao, J.; Guo, Y.; Feng, T.; Rong, D.; Kong, X.; Huang, T.; Lopez-Lopez, V.; Yarmohammadi, H.; Sakamoto, Y.; Zhu, D.; et al. Efficacy and safety of regorafenib in combination with immune checkpoint inhibitor therapy as second-line and third-line regimen for patients with advanced hepatocellular carcinoma: A retrospective study. J. Gastrointest. Oncol. 2023, 14, 2549–2558. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Lai, K.C.; Hsu, T.L.; Lin, S.Y.; Chiang, N.J.; Chen, M.; Chao, Y.; Yang, M.H.; Chen, S.C. Real-world efficacy of cabozantinib alone or in combination with ICIs in heavily pretreated hepatocellular carcinoma: Potential role of AXL and MET expression: Cabozantinib ± ICIs in pretreated HCC patients. Ann. Hepatol. 2025, 30, 101917. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  50. Hsu, C.; Chang, Y.F.; Yen, C.J.; Xu, Y.W.; Dong, M.; Tong, Y.Z. Combination of GT90001 and nivolumab in patients with advanced hepatocellular carcinoma: A multicenter, single-arm, phase 1b/2 study. BMC Med. 2023, 21, 395. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  51. Zhu, A.X.; Kang, Y.K.; Yen, C.J.; Finn, R.S.; Galle, P.R.; Llovet, J.M.; Assenat, E.; Brandi, G.; Pracht, M.; Lim, H.Y.; et al. Ramucirumab after sorafenib in patients with advanced hepatocellular carcinoma and increased α-fetoprotein concentrations (REACH-2): A randomised, double-blind, placebo-controlled, phase 3 trial. Lancet Oncol. 2019, 20, 282–296. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  52. Kudo, M.; Ueshima, K.; Ikeda, M.; Torimura, T.; Tanabe, N.; Aikata, H.; Izumi, N.; Yamasaki, T.; Nojiri, S.; Hino, K.; et al. Final Results of TACTICS: A Randomized, Prospective Trial Comparing Transarterial Chemoembolization Plus Sorafenib to Transarterial Chemoembolization Alone in Patients with Unresectable Hepatocellular Carcinoma. Liver Cancer 2022, 11, 354–367. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  53. Peng, Z.; Fan, W.; Zhu, B.; Wang, G.; Sun, J.; Xiao, C.; Huang, F.; Tang, R.; Cheng, Y.; Huang, Z.; et al. Lenvatinib Combined with Transarterial Chemoembolization as First-Line Treatment for Advanced Hepatocellular Carcinoma: A Phase III, Randomized Clinical Trial (LAUNCH). J. Clin. Oncol. 2023, 41, 117–127. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  54. Ben Khaled, N.; Seidensticker, M.; Ricke, J.; Mayerle, J.; Oehrle, B.; Rössler, D.; Teupser, D.; Ehmer, U.; Bitzer, M.; Waldschmidt, D.; et al. Atezolizumab and bevacizumab with transarterial chemoembolization in hepatocellular carcinoma: The DEMAND trial protocol. Future Oncol. 2022, 18, 1423–1435. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  55. Sangro, B.; Kudo, M.; Erinjeri, J.P.; Qin, S.; Ren, Z.; Chan, S.L.; Arai, Y.; Heo, J.; Mai, A.; Escobar, J.; et al. Durvalumab with or without bevacizumab with transarterial chemoembolisation in hepatocellular carcinoma (EMERALD-1): A multiregional, randomised, double-blind, placebo-controlled, phase 3 study. Lancet 2025, 405, 216–232. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  56. Llovet, J.M.; Vogel, A.; Madoff, D.C.; Finn, R.S.; Ogasawara, S.; Ren, Z.; Mody, K.; Li, J.J.; Siegel, A.B.; Dubrovsky, L.; et al. Randomized Phase 3 LEAP-012 Study: Transarterial Chemoembolization with or Without Lenvatinib Plus Pembrolizumab for Intermediate-Stage Hepatocellular Carcinoma Not Amenable to Curative Treatment. Cardiovasc. Interv. Radiol. 2022, 45, 405–412. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  57. Duffy, A.G.; Ulahannan, S.V.; Makorova-Rusher, O.; Rahma, O.; Wedemeyer, H.; Pratt, D.; Davis, J.L.; Hughes, M.S.; Heller, T.; ElGindi, M.; et al. Tremelimumab in combination with ablation in patients with advanced hepatocellular carcinoma. J. Hepatol. 2017, 66, 545–551. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  58. Tai, D.; Loke, K.; Gogna, A.; Kaya, N.A.; Tan, S.H.; Hennedige, T.; Ng, D.; Irani, F.; Lee, J.; Lim, J.Q.; et al. Radioembolisation with Y90-resin microspheres followed by nivolumab for advanced hepatocellular carcinoma (CA 209-678): A single arm, single centre, phase 2 trial. Lancet Gastroenterol. Hepatol. 2021, 6, 1025–1035. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  59. Ding, M.; Wang, Y.; Chi, J.; Wang, T.; Tang, X.; Cui, D.; Qian, Q.; Zhai, B. Is Adjuvant Cellular Immunotherapy Essential after TACE-Predominant Minimally Invasive Treatment for Hepatocellular Carcinoma? A Systematic Meta-Analysis of Studies Including 1774 Patients. PLoS ONE 2016, 11, e0168798. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  60. Dawson, L.A.; Winter, K.A.; Knox, J.J.; Zhu, A.X.; Krishnan, S.; Guha, C.; Kachnic, L.A.; Gillin, M.T.; Hong, T.S.; Craig, T.D.; et al. Stereotactic Body Radiotherapy vs Sorafenib Alone in Hepatocellular Carcinoma: The NRG Oncology/RTOG 1112 Phase 3 Randomized Clinical Trial. JAMA Oncol. 2025, 11, 136–144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  61. de la Torre-Aláez, M.; Matilla, A.; Varela, M.; Iñarrairaegui, M.; Reig, M.; Lledó, J.L.; Arenas, J.I.; Lorente, S.; Testillano, M.; Márquez, L.; et al. Nivolumab after selective internal radiation therapy for the treatment of hepatocellular carcinoma: A phase 2, single-arm study. J. Immunother. Cancer 2022, 10, e005457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  62. Kim, B.H.; Park, H.C.; Kim, T.H.; Koh, Y.H.; Hong, J.Y.; Cho, Y.; Sinn, D.H.; Park, B.; Park, J.W. Concurrent nivolumab and external beam radiation therapy for hepatocellular carcinoma with macrovascular invasion: A phase II study. JHEP Rep. 2024, 6, 100991. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  63. Kumar, R.; Yadav, H.P.; Thaper, D.; Kamal, R.; Gupta, A.; Kirti, S. Efficacy and toxicity of SBRT in advanced hepatocellular carcinoma with portal vein tumor thrombosis—A retrospective study. Rep. Pract. Oncol. Radiother. 2021, 26, 573–581. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  64. Zhou, Y.; Wei, S.; Xu, M.; Wu, X.; Dou, W.; Li, H.; Zhang, Z.; Zhang, S. CAR-T cell therapy for hepatocellular carcinoma: Current trends and challenges. Front. Immunol. 2024, 15, 1489649. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  65. Zhou, F.; Shang, W.; Yu, X.; Tian, J. Glypican-3: A promising biomarker for hepatocellular carcinoma diagnosis and treatment. Med. Res. Rev. 2018, 38, 741–767. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  66. Yang, H.; Liu, Y.; Zhang, N.; Tao, F.; Yin, G. Therapeutic advances in hepatocellular carcinoma: An update from the 2024 ASCO annual meeting. Front. Oncol. 2024, 14, 1453412. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  67. Vercher, E.; Covo-Vergara, Á.; Conde, E.; Hernández-Rueda, M.; Elizalde, E.; Mancheño, U.; Glez-Vaz, J.; Tamayo-Uria, I.; García-García, M.R.; Ferrer-Roig, M.; et al. Human T cells engineered with an HLA-A2-restricted murine T-cell receptor targeting glypican 3 effectively control human hepatocellular carcinoma in mice. Hepatology 2025, 82, 326–343. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  68. Pang, N.; Shi, J.; Qin, L.; Chen, A.; Tang, Y.; Yang, H.; Huang, Y.; Wu, Q.; Li, X.; He, B.; et al. IL-7 and CCL19-secreting CAR-T cell therapy for tumors with positive glypican-3 or mesothelin. J. Hematol. Oncol. 2021, 14, 118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  69. Zhang, J.; Li, R.; Tan, X.; Wang, C. Targeting Glypican-3 for Liver Cancer Therapy: Clinical Applications and Detection Methods. J. Clin. Transl. Hepatol. 2025, 13, 665–681. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  70. Lee, J.Y.; Lee, J.; Kim, S.; Yoo, J.-S.; Kim, J.H.; Yang, K.; Han, J.W.; Jang, J.W.; Choi, J.Y.; Yoon, S.K.; et al. Improved survival with second-line hepatic arterial infusion chemotherapy after atezolizumab-bevacizumab failure in hepatocellular carcinoma. Front. Oncol. 2024, 14, 1495321. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  71. Zhao, H.; Zhang, X.; Tian, P.; Luo, Y.; Sun, W.; Li, Y.; Li, J.; Gong, T.; Yang, Z.; Song, P.; et al. Hepatic arterial infusion chemotherapy plus regorafenib compared with regorafenib alone as second-line therapy for advanced hepatocellular carcinoma: A randomised controlled trial protocol. BMJ Open 2024, 14, e080805. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  72. Sindhu, K.K.; Nehlsen, A.D.; Lehrer, E.J.; Rowley, J.P.; Stock, R.G.; Galsky, M.D.; Buckstein, M. Oligoprogression of Solid Tumors on Immune Checkpoint Inhibitors: The Impact of Local Ablative Radiation Therapy. Biomedicines 2022, 10, 2481. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. Visual abstract of our algorithm for management of metastatic HCC- Created in Biorender.com. Our proposed algorithm for management of metastatic or advanced unresectable HCC. Following progression on ICI-based combinations, most patients transition to tyrosine kinase inhibitors such as lenvatinib or cabozantinib. Clinical trial participation is highly encouraged when available. * ICI rechallenge is not supported by high-level evidence and not routinely recommended after progression on prior immunotherapy, and should be explored in the context of clinical trials or highly selected patients. ICI—immune checkpoint inhibitor, LRT—locoregional therapy, TKI—tyrosine kinase inhibitor, HCC—hepatocellular carcinoma, AFP—alpha-fetoprotein, TACE—Transarterial chemoembolization. Category 1 based on high-level evidence. Category 2A and 2B based on lower-level evidence.
Livers 06 00085 g001
Table 3. Ongoing clinical trials on CAR-T in metastatic HCC.
Study/TrialStudy DesignStudy Population/InterventionKey Outcomes/Endpoints
NCT05003895Phase I clinical trialAdvanced HCC expressing GPC3 (≥25% by IHC), Child–Pugh A, ECOG 0–1, ≥1 measurable lesion; second-line treatment with anti-GPC3 CAR (hYP7) T cellsPrimary objectives: determination of maximum tolerated dose (MTD), dose-limiting toxicities (DLTs), safety, and feasibility of anti-GPC3 CAR-T cells; secondary objectives include best overall response and overall survival.
NCT03198546Phase I, open-label, nonrandomized, single-arm studyAdvanced HCC and other solid tumors (pancreatic and ovarian cancer) expressing GPC3 or mesothelin; IL-7 plus CCL19 (“7 × 19”) armored CAR-T cellsPrimary objectives: safety and feasibility; secondary objectives assess CAR-T expansion, migration, persistence, tumor infiltration, and preliminary antitumor activity compared with conventional CAR-T cells.
ATHENA (NCT06084884)First-in-human, single-arm, open-label, multicenter phase I/II studyAdults with GPC3-positive advanced, recurrent, metastatic, or unresectable HCC; ECOG 0–1, Child–Pugh A; ≥1 prior line of systemic therapyPrimary endpoints: safety and tolerability; secondary endpoints include ORR, best overall response, duration of response, DCR, PFS, OS, and pharmacokinetics; exploratory endpoints evaluate pharmacodynamic biomarkers, immune cell kinetics, and immunogenicity.
OS—overall survival, PFS—progression-free survival, DCR—disease control rate, ORR—overall response rate, CAR-T—chimeric antigen receptor T cell, GPC—Glypican, CCL-19—C-C motif chemokine ligand 19, HCC—hepatocellular carcinoma.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.