Review

Hydrogel-Forming Microneedles for Interstitial-Fluid Biosensing and Therapeutic Monitoring

by
Hossein Omidian
* and
Sumana Dey Chowdhury
Department of Pharmaceutical Sciences, Barry and Judy Silverman College of Pharmacy, Nova Southeastern University, Fort Lauderdale, FL 33328, USA
*
Author to whom correspondence should be addressed.
J. Nanotheranostics 2026, 7(3), 19; https://doi.org/10.3390/jnt7030019
Submission received: 25 June 2026 / Revised: 18 July 2026 / Accepted: 3 August 2026 / Published: 5 August 2026

Abstract

Hydrogel-forming microneedles (HFMNs) are minimally invasive interfaces that access interstitial fluid (ISF) through skin penetration, swelling-mediated uptake, analyte diffusion, and hydrated sensor integration. This review examines HFMN architectures, skin–device interfaces, ISF transport, molecular-recognition and signal-transduction strategies, analytical performance, benchmarking, wear-associated failure modes, therapeutic monitoring, and translational priorities. The field has expanded from glucose sensing to metabolites, ions, hormones, proteins, nucleic acids, microbial and wound biomarkers, and therapeutic drugs, enabled by advances in hydrogel chemistry, conductive networks, nanostructured electrodes, catalysis, affinity recognition, molecular imprinting, optical readouts, and multiplexed wearables. Performance remains context dependent and requires physiological range, calibration stability, biofouling resistance, reliable insertion, validated ISF-reference correlations, and interpretable thresholds. Evidence is strongest in artificial matrices, ex vivo tissue, and animals, while human validation remains limited. Translation will require standardized mechanics and transport reporting, longer wear studies, sterilization-compatible chemistries, scalable manufacturing, and clinical validation. HFMNs may complement rather than replace blood-based diagnostics.

Graphical Abstract

1. Introduction

Continuous biochemical monitoring has transformed diabetes care, yet the broader promise of minimally invasive molecular surveillance remains largely unrealized. Blood remains the dominant clinical matrix for therapeutic drug monitoring, metabolic assessment, and biomarker quantification, but repeated sampling is poorly suited to continuous, ambulatory, or decentralized care. ISF, occupying the extracellular space beneath the skin, offers a compelling alternative because it reflects local and systemic physiology and is accessible through shallow, minimally invasive interfaces. Microneedles have therefore become central to wearable biosensors that sample or interrogate dermal ISF without conventional venipuncture [1,2,3].
Within this landscape, HFMNs represent a particularly important architectural class. Their significance lies not only in painless or minimally invasive skin access, but also in functioning as hydrated polymeric interfaces that couple penetration, fluid uptake, analyte diffusion, receptor stabilization, and sensor integration. Poly(ethylene glycol) diacrylate (PEGDA) extraction arrays, methacrylated hyaluronic acid (MeHA)/poly(vinyl alcohol) (PVA) hydrogel patches, conductive hyaluronic acid systems, and highly swellable microneedle–electrode platforms illustrate how hydrogel composition and geometry can support ISF acquisition and on-device analysis [4,5,6,7]. Conductive and composite hydrogels further transform the microneedle matrix from a passive sampler into an active transduction environment, as demonstrated by poly(3,4-ethylenedioxythiophene):poly(styrenesulfonate) (PEDOT:PSS)-containing hydrogel electrodes, MeHA/PEDOT:PSS/graphene oxide microneedles, and MXene-containing hydrogel wound dressings [5,8,9].
The biological scope of microneedle sensing has expanded substantially. Early work established glucose as the dominant benchmark analyte, with enzymatic, nonenzymatic, porous, hollow, and high-density microneedle systems demonstrating ISF glucose detection and several showing correlations with blood or commercial glucometer measurements [10,11,12,13,14,15]. More recent hydrogel and hydrogel-relevant platforms have broadened the field to lactate, urea, uric acid, ketones, potential of hydrogen (pH), electrolytes, insulin, immunoglobulin E (IgE), protein biomarkers, nucleic acids, and wound-associated biomarkers [4,8,16,17,18,19,20]. This diversification is critical because HFMNs’ clinical value will depend on supporting analytes that are difficult to monitor continuously with conventional wearable technologies.
Molecular recognition has evolved alongside this analyte expansion. Enzymatic systems remain the most mature route for metabolite sensing, particularly when catalytic specificity and established biochemical pathways can be coupled to electrochemical readout [10,15,21,22,23,24]. However, affinity-based recognition is increasingly central to therapeutic and disease-state monitoring. Aptamer-based platforms have enabled monitoring of insulin, IgE, cortisol, phenylalanine, vancomycin, gentamicin, tobramycin, and infection-associated response markers not easily addressed by classical enzyme chemistry [25,26,27,28,29,30,31]. Immunochemical and hydrogel-protected recognition systems further demonstrate feasible protein biomarker monitoring, including insulin and other clinically relevant macromolecules [18,32,33,34,35]. These advances suggest that HFMNs may ultimately support personalized biochemical monitoring beyond the metabolic domain.
Therapeutic drug monitoring is among the field’s most clinically consequential directions. Hydrogel microneedle systems have generated real-time antibiotic profiles, including vancomycin and gentamicin monitoring, while aptameric microneedle patches have shown strong ISF–blood correlation for tobramycin and vancomycin [28,29]. Related platforms have extended drug monitoring to lidocaine, buprenorphine, olanzapine, fentanyl, methylene blue, mitoxantrone, irinotecan, and related pharmacokinetic targets [6,36,37,38,39,40]. These studies indicate that microneedle-accessed ISF may provide actionable pharmacokinetic information, but also underscore that ISF cannot be treated as a universal blood surrogate. Drug-specific blood–ISF partitioning, tissue access, distribution, and local or organ-level clearance must be defined before ISF measurements can support dosing decisions [39,40].
The most ambitious frontier is the convergence of sensing and therapy. Several platforms approach theranostic functionality by combining monitoring with drug release, stimulation, or wound management. A bilayer microneedle–triboelectric platform integrated antibiotic release, electrical stimulation, and wound-biomarker monitoring [41]. A biomimetic diabetes theranostic system linked glucose and ion sensing to insulin delivery [42]. A hydrogel-forming wound dressing combined wound-ISF biomarker monitoring with antimicrobial and therapeutic functions [8]. These examples establish a plausible path from passive biosensing to feedback-informed intervention, although they remain early demonstrations rather than evidence of broadly validated closed-loop HFMN therapy [1,3].
Translation now requires a shift in emphasis. The field has generated impressive sensing modalities, material platforms, and analyte panels, but clinical readiness depends on more than technical novelty. HFMN systems must function stably during hydration, motion, and biological fouling; preserve receptor activity after fabrication and sterilization; maintain mechanical reliability during insertion and removal; generate interpretable signals across relevant patient populations; and align ISF outputs with accepted clinical comparators [1,2,3,18,43,44]. The central question is no longer whether microneedles can access ISF or detect biomarkers, but whether HFMNs can become reliable, manufacturable, clinically interpretable interfaces for continuous monitoring and therapeutic decision-making.

2. Scope, Classification, and Therapeutic Relevance

2.1. Defining the Review Scope

This review focuses on HFMNs as soft, polymeric interfaces for ISF biosensing and therapeutic monitoring. HFMNs are distinct from hollow microneedles (HMNs), although the broader literature sometimes uses HMNs ambiguously to refer to hydrogel-forming or hollow microneedles. In this manuscript, HFMNs refer only to hydrogel-forming microneedles, and HMNs only to hollow microneedles. HFMNs use hydrated or swellable polymer networks to interface with ISF, whereas HMNs use lumen- or channel-based fluid transport [5,19,45]. This distinction is essential because much of the broader microneedle biosensing literature is relevant to ISF monitoring but does not constitute direct evidence for HFMNs.
The strongest evidence for the central theme comes from hydrogel-forming, hydrogel-integrated, swellable, conductive-hydrogel, or hydrogel-coated microneedle systems that enable ISF access and biomarker monitoring. These platforms monitor clinically relevant metabolites, proteins, electrolytes, nucleic acids, microbial targets, drugs, and wound biomarkers in ISF or tissue-associated fluids [8,16,18,19,20,28,46]. The field has thus progressed beyond proof-of-concept glucose sensing to broader biochemical surveillance, including insulin monitoring for diabetes-related therapeutic assessment [18], ketone monitoring for diabetic ketoacidosis risk management [19], C-reactive protein (CRP) tracking during resistant infection and vancomycin treatment [30], and multiplex wound-biomarker monitoring [8]. Nevertheless, most HFMN-based sensing systems remain diagnostic or monitoring platforms rather than integrated therapeutic devices. Their translational value lies primarily in providing timely biochemical information that could inform clinical decisions, rather than autonomous treatment control [8,19,28,30].

2.2. Hydrogel-Integrated and Hydrogel-Relevant Sensing Platforms

A second evidence tier comprises hydrogel-relevant systems that use hydrogel coatings, gel shells, PEGDA matrices, swellable polymers, hydrogel transducers, or gel-mediated sensing interfaces without always meeting the stricter HFMN definition. These platforms clarify how hydrated polymer interfaces support ISF uptake, analyte access, signal stability, or wearable integration. Examples include PEGDA-associated sensing systems [4,47], metal–hydrogel-assisted immunoglobulin G (IgG) monitoring [17], gel microneedles for self-powered monitoring and short-term forecasting of glucose, lactate, and uric acid [48], glucose-responsive polymer-coated microneedles [49], methacrylated hyaluronic acid microneedles for glucose extraction [50], hydrogel-coated surface-enhanced Raman scattering (SERS) microneedles for drug monitoring [39], hydrogel-coated glucose biosensors and hydrogel-containing core–shell microneedle biosensors [22,44], and swellable or hydrogel-mediated systems for glucose, alcohol, cortisol, and ion monitoring [7,31,51].
Together, this group shows that hydrogel functionality often improves sampling or sensing rather than enabling therapy. Hydrogel integration should not be equated with drug delivery, feedback control, or closed-loop treatment unless those functions are explicitly demonstrated. In the current evidence base, hydrogel-containing microneedles more consistently support ISF biosensing than therapeutic intervention [1,2].

2.3. Comparator Microneedle Biosensors and the ISF Monitoring Landscape

Comparator microneedle biosensors provide necessary context but should not dilute the manuscript’s HFMN focus. Hollow, porous, polymeric, SERS-active, aptameric, clustered regularly interspaced short palindromic repeats (CRISPR)-functionalized, molecularly imprinted, metallic/nanostructured, and other electrochemical microneedles have been reported across diverse ISF-relevant biomarkers [45,52,53,54,55,56,57]. These include metabolic and ionic targets such as glucose, lactate, ketones/acetoacetate, urea, uric acid, pH, and electrolytes [21,52,55,58,59,60,61]. Dedicated electrochemical microneedle systems also support oxygen and hydrogen peroxide monitoring [62,63]. Additional comparator platforms address cortisol, dopamine/catecholamines, cytokines, cancer markers, nucleic acids, bacteria, and endotoxins [34,53,56,57,64,65,66]. Drug-focused examples include lidocaine, buprenorphine, olanzapine, fentanyl, methotrexate, and pharmacokinetic or drug-clearance monitoring [6,36,37,38,40,67]. Collectively, these studies show microneedle biosensing expanding from single-analyte metabolic tracking to multiplexed and disease-specific monitoring.
Their relevance is comparative rather than central. They identify analytes, sampling strategies, and translational use cases that HFMNs may also address but do not establish the advantages of HFMN architectures. Comparator systems often emphasize electrode performance, hollow-channel sampling, metallic transduction, molecular recognition, or nanostructured sensing rather than hydrogel-mediated ISF uptake, analyte diffusion, biocompatibility, or coupling with drug-release functions. Accordingly, they are most useful for defining what HFMN platforms must match or improve: reliable ISF access, selectivity in complex matrices, long-wear stability, biofouling resistance, and clinically meaningful interpretation of sensor outputs [1,2,52,62].

2.4. Therapeutic Monitoring and Drug-Delivery Relevance

The therapeutic-monitoring literature provides the most important bridge between ISF biosensing and dosing- or treatment-decision-making. Studies targeting vancomycin, gentamicin, tobramycin, infection-associated CRP dynamics, and drug pharmacokinetic or clearance interpretation are especially aligned with this transition because they connect microneedle sampling to pharmacokinetic assessment, treatment-response evaluation, or precision dosing [28,29,30,40]. Other platforms extend microneedle-based drug monitoring to lidocaine overdose prevention [36], buprenorphine monitoring [37], olanzapine monitoring [38], fentanyl detection [6], 3,4-methylenedioxymethamphetamine (MDMA) toxicology tracking [68], methylene blue and mitoxantrone pharmacokinetics [39], rhodamine 6G model pharmacokinetic profiling [69], and electrochemical aptamer-based monitoring of non-redox-active molecular targets [70].
This body of work supports the premise that ISF-accessing microneedles can contribute to therapeutic monitoring but also exposes a major limitation: most platforms measure drug levels or treatment-associated biomarkers without showing that sensor outputs directly control dosing, release, or therapeutic adjustment. Only a smaller subset approaches monitoring–intervention integration. A bilayer microneedle–triboelectric platform integrates antibiotic release, electrical stimulation, and wound-biomarker monitoring [41]. A biomimetic diabetes theranostic platform couples glucose and physiological-ion sensing with subcutaneous insulin delivery [42]. A hydrogel-forming microneedle wound dressing links wound-ISF biomarker monitoring with intelligent wound management [8]. These examples define the field’s therapeutic frontier but should be interpreted as early integrated or theranostic platforms, not as evidence that mature HFMN-based closed-loop therapy has been broadly achieved.

2.5. Peripheral and Framework Evidence

Frameworks and reviews help define translational requirements for continuous microneedle monitoring, therapeutic drug monitoring, closed-loop integration, active-reset strategies, and HFMN-based sensing development [1,2,3,43]. These sources organize the field but should not be weighted as primary experimental evidence. Peripheral microneedle studies in saliva, sweat, intracellular environments, plant fluids, food matrices, and fish tissue further illustrate the adaptability of microneedle-based analytical formats [71,72,73,74,75,76,77]. Fish-tissue hypoxanthine monitoring is useful as a nonclinical electrochemical sensing comparator but remains outside the central axis of HFMNs, ISF, and therapeutic monitoring [77].
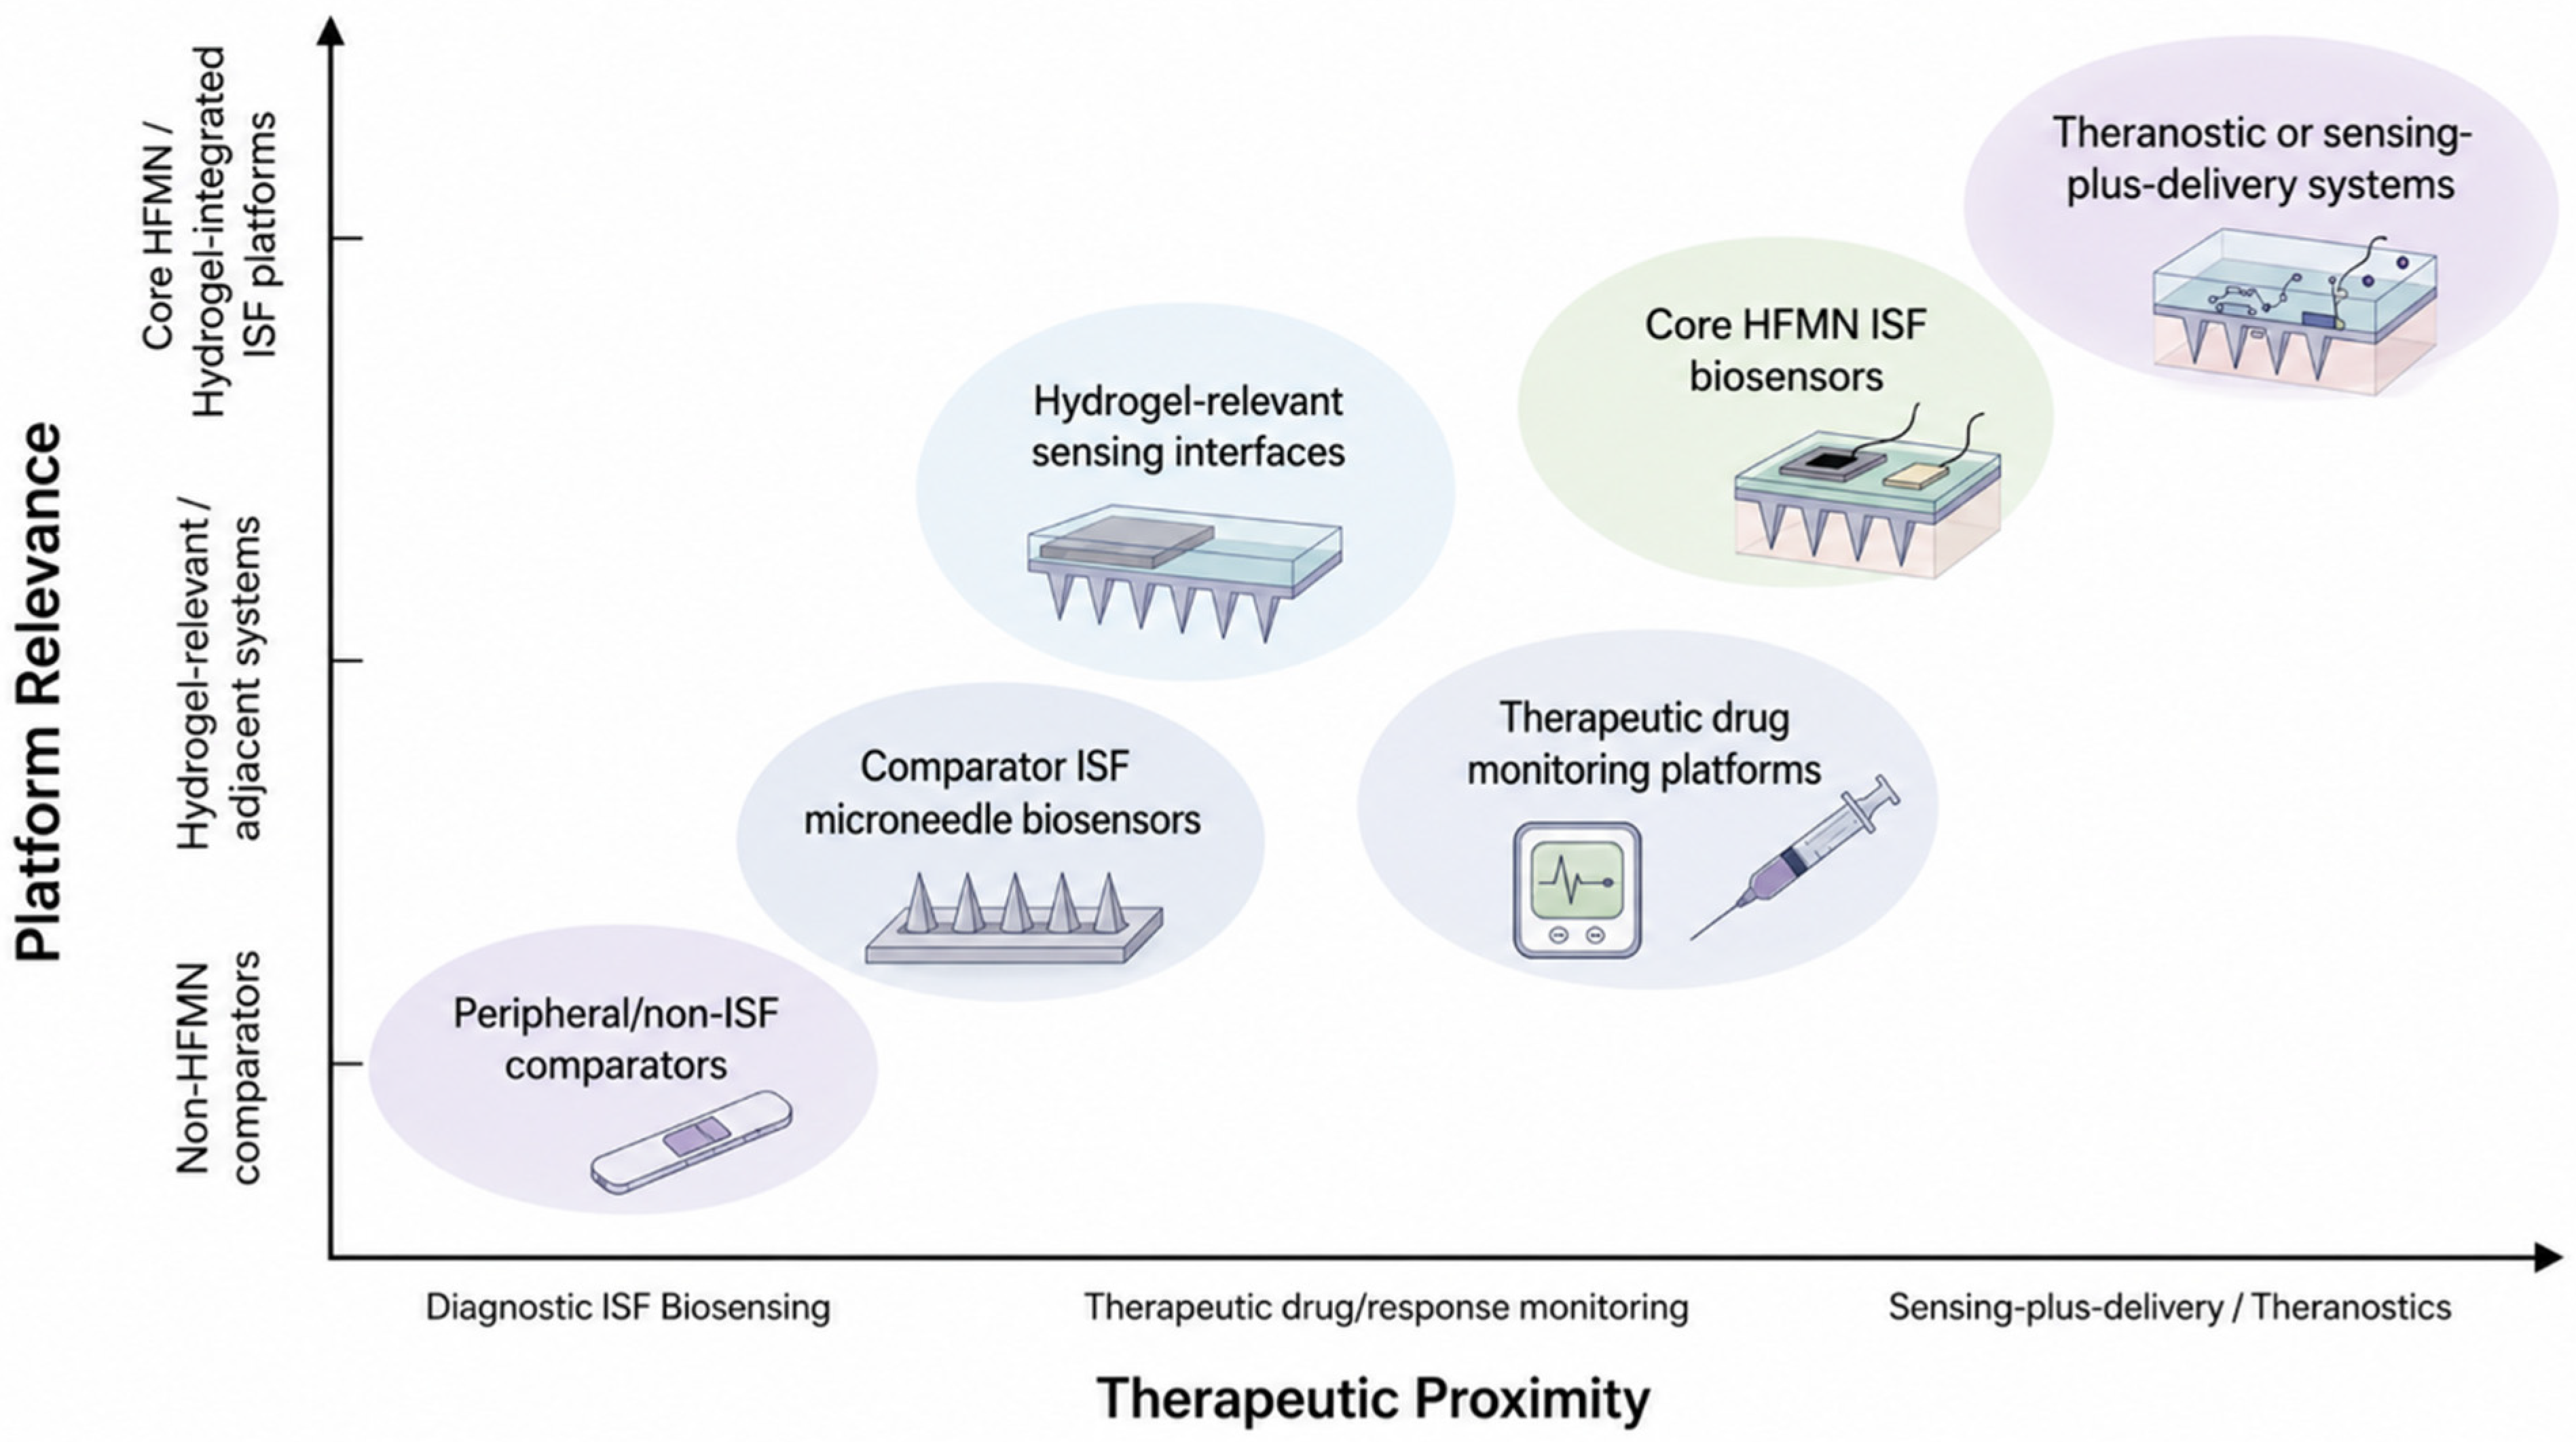
Overall, the evidence supports a clear hierarchy. HFMNs and hydrogel-integrated platforms provide the strongest foundation for ISF biosensing. Hydrogel-relevant systems clarify how hydrated interfaces enhance sampling or sensing. Comparator microneedle biosensors define the broader analytical landscape and performance expectations. Therapeutic-monitoring platforms show the clinical value of ISF drug and biomarker tracking. True sensing-plus-delivery systems remain comparatively limited, indicating progression from minimally invasive ISF biosensing toward therapeutic monitoring, while robust HFMN-enabled closed-loop therapy remains an emerging rather than established capability [8,41,42,67]. This evidence positioning is summarized in Table 1 and conceptualized in Figure 1.

3. Microneedle Architecture, Skin Interface, ISF Access, and Transport Behavior

3.1. Hydrogel-Forming and Swellable Microneedles as ISF-Access Interfaces

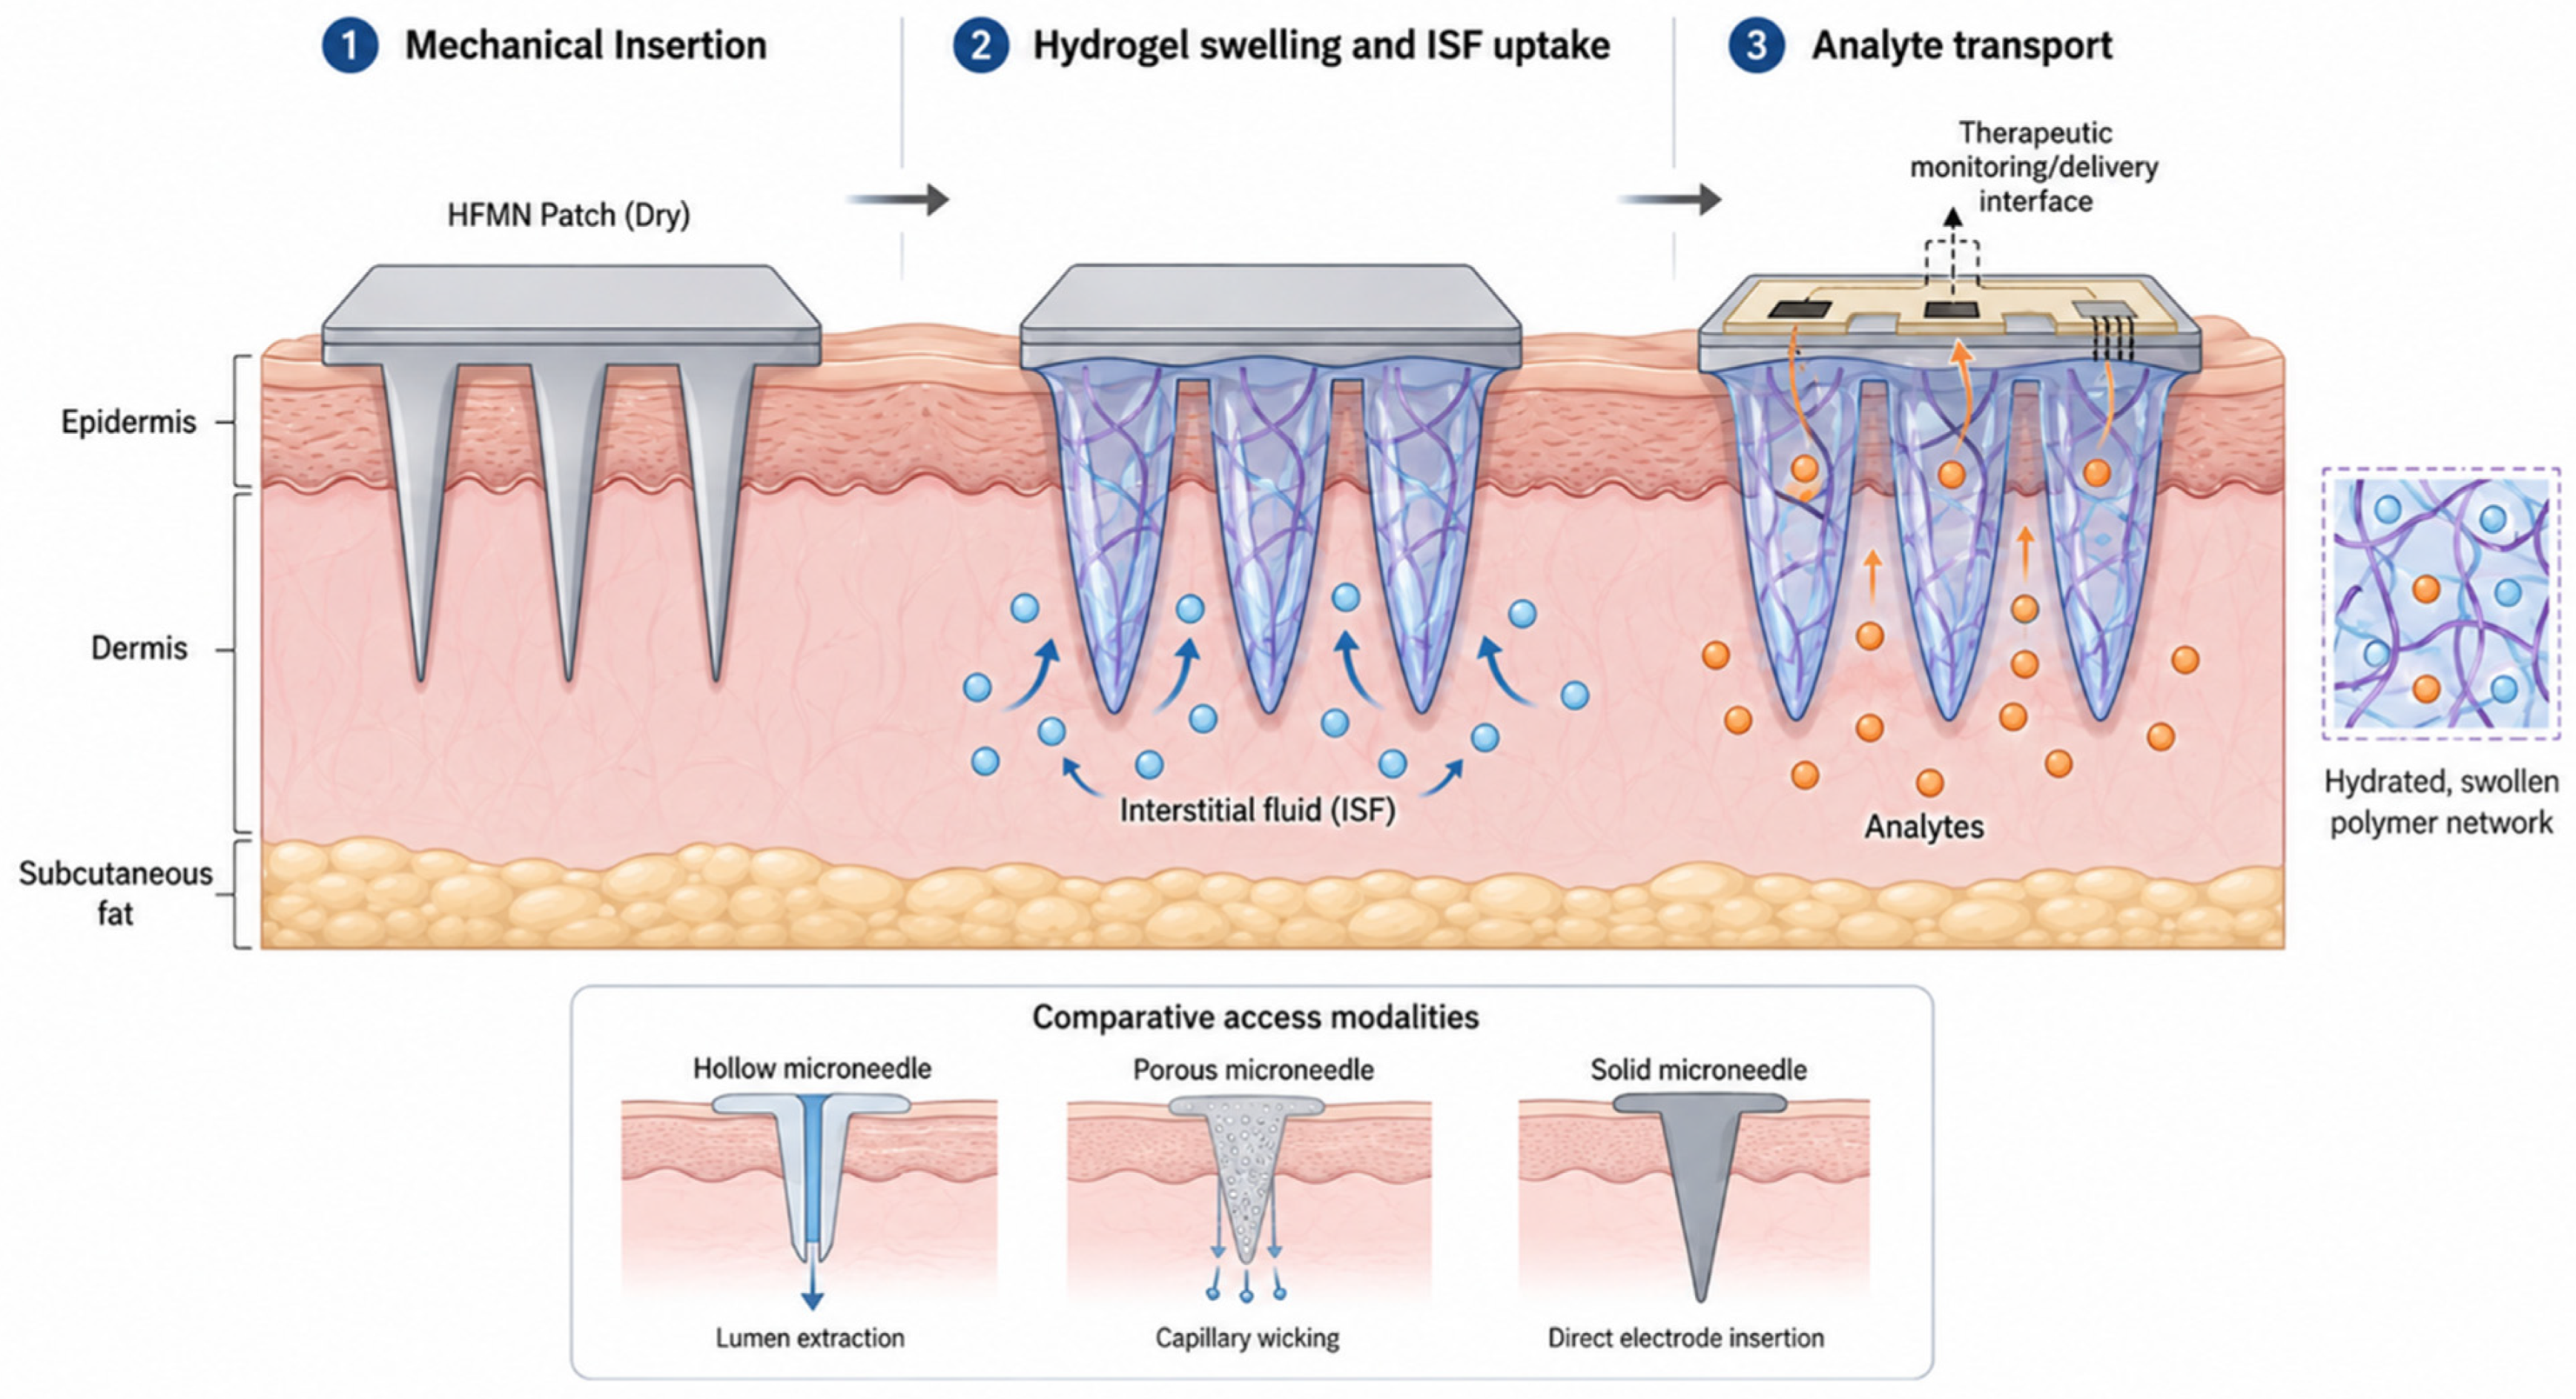
Hydrogel-forming and swellable microneedles are the architectural core of this review because they combine skin penetration with fluid uptake through hydrated polymer networks. Their advantage is minimal invasiveness combined with simultaneous function as temporary skin-access structures and ISF-collecting matrices. This distinguishes HFMNs from HMNs, which typically route fluid through a lumen, and solid microneedles, which primarily position an electrode or sensing surface within the skin. Figure 2 illustrates the architecture-controlled sequence of dry insertion, hydrogel swelling, ISF uptake, and analyte transport.
The strongest architectural evidence for HFMNs, hydrogel-integrated microneedles, and hydrogel-mediated sampling comes from systems explicitly reporting swelling capacity, insertion force, extracted volume, or needle geometry. PEGDA microneedles were fabricated as a 10 × 10 extraction array with an average needle length of 782 ± 10 µm [4]. MeHA/PVA composite hydrogel microneedles exhibited mechanical strength exceeding 0.1 N per needle and 400% swelling [6]. Highly swellable microneedles coupled to electrode arrays extracted approximately 6.87 µL per needle within 5 min while maintaining a penetration strength of 0.21 N per needle [7]. A two-layer swellable patch absorbed 60.2 mg of ISF within 10 min in vitro [80]. These data support hydrogel-mediated ISF acquisition but also show that the field lacks a common framework for comparing swelling, insertion strength, uptake kinetics, and post-insertion integrity across formulations.
Material evidence is promising but uneven. MeHA repeatedly serves as a swellable ISF-extracting matrix in MeHA-based extraction patches, MeHA/PVA composites, MeHA matrices for probe loading, and MeHA systems incorporating graphene oxide–probe conjugates [6,20,31,50]. Other HFMN or hydrogel-integrated formulations include gelatin methacryloyl (GelMA) microneedles [78], hyaluronic acid methacryloyl/sodium hyaluronate microneedles [30], PEGDA microneedles [4], and PVA/chitosan hydrogel dressings [8]. However, most summaries do not report crosslinking density or directly relate network structure to mechanical strength, swelling, analyte diffusion, or drug-release behavior. Thus, the evidence supports the importance of hydrogel composition but does not permit rigorous formulation-level comparison of how network structure governs ISF uptake or transport.
Conductive hydrogels provide a more integrated architecture in which the hydrogel is both the sampler and the sensing interface. Dopamine-conjugated hyaluronic acid containing PEDOT:PSS enabled on-needle ISF pH measurement, and the effect of PEDOT:PSS on swelling and mechanical strength was specifically evaluated [5]. A crosslinked MeHA/PEDOT:PSS/graphene oxide composite formed sharp hydrogel microneedles that functioned directly as working electrodes [9]. A PVA/chitosan/MXene hydrogel-forming wound dressing integrated PEDOT:PSS/graphene oxide electrodes on the HFMNs and reached a conductivity of 384 S/m [8]. These examples show progression from passive sampling to integrated hydrogel–electrode systems. However, the evidence remains insufficient to compare PEDOT:PSS, graphene oxide, and MXene for long-term skin exposure, cytocompatibility, or hydration-dependent drift within this architecture section.

3.2. HMN, Core–Shell, and Protected Sampling Designs

HMNs offer a parallel but mechanistically distinct approach to ISF access. Instead of absorbing ISF into a swelling matrix, they create dermal conduits that transfer fluid through a lumen, inner cavity, or coupled collection/sensing module. A touch-activated HMN system generated negative pressure as low as approximately −53 kPa and extracted ISF at approximately 2 µL per needle per hour [45]. Other HMN platforms used finger-activated pumping, custom collection chambers, microvalves, vacuum tubes, capillary uptake, or passive capillary filling for ISF extraction or sensing [14,17,47,58,81]. A single hollow silicon microneedle integrated a sensing probe inside the lumen; molecular diffusion carried glucose to the sensing region, with an approximately 10 min physiological delay observed in human forearm testing [14]. Three HMNs continuously coupled dermal ISF to an external molecular sensor, producing a 20 min lag time in human monitoring [27].
These studies define useful benchmarks for HFMN sampling efficiency and lag time but should not be conflated with hydrogel-forming systems. HMNs often address ISF availability through pressure, lumen geometry, capillary filling, or coupled collection modules, whereas HFMNs rely primarily on swelling, hydration, and matrix transport. They are most valuable for assessing whether HFMNs can achieve comparable ISF access without pumps, vacuum systems, or open channels.
Core–shell and cavity-protected structures address a recurring microneedle-biosensing limitation: preservation of the sensing interface during insertion. A hollow outer shell surrounding a sensing core reduced damage to the active region [82], while recessed microcavities at microneedle tips protected sensing layers from delamination during insertion and removal [83]. A high-molecular-weight poly(lactic acid) (PLA) hollow shell filled with zwitterionic hydrogel isolated the internal sensing layer from subcutaneous friction while preserving epidermal penetration strength [44]. These architectures show that mechanical protection is becoming as important as sampling efficiency, particularly for prolonged wear and repeated insertion.

3.3. Porous, Capillary, Osmotic, and Microchannel-Mediated Transport

Porous and channel-engineered microneedles show how architecture can increase passive ISF access without bulk hydrogel swelling. Porous microneedles paired with poly(ethylene glycol) (PEG)-loaded filter paper physically separated ISF extraction from transduction and reduced insertion-related coating damage [52]. Ethoxylated trimethylolpropane triacrylate (ETPTA) porous microneedles extracted ISF by capillary action without post-processing and provided a specific surface area of 6.694 m2/g [66]. Macroporous-channel HMNs combined a rigid shell, interconnected pores, and an axial lumen to drive multiscale capillarity, transferring ISF to paper-wick collectors with extraction behavior comparable to that of negative-pressure systems [60]. Bioinspired hierarchical microchannel microneedles likewise used capillary action to enhance ISF collection [84].
Across these studies, porosity, capillarity, and channel hierarchy can partially substitute for external actuation. Osmosis-assisted HMNs used magnesium chloride (MgCl2) to enhance ISF withdrawal [55], while ultrasharp microneedles with base reservoirs and open side channels supported ISF collection from the skin-entry site toward reservoir regions [36]. These strategies highlight principles compatible with swelling hydrogels, including capillary amplification, short transport distances, and compartmentalized routing. However, many porous, hollow, or channel-engineered systems remain analytical sampling devices rather than hydrogel-forming matrices; their translational relevance to HFMNs therefore depends on integrating the transport mechanism without compromising hydrogel insertion strength or hydration behavior.

3.4. Solid, Metallic, Polymeric, and Nanocomposite Microneedle Interfaces

Solid, coated, and other non-HFMN microneedles are not central to this manuscript but clarify what HFMNs must match or improve: reliable penetration, stable ISF contact, minimal tissue trauma, and durable sensor integration. Reported examples include a microneedle electrode array measuring 600 × 100 × 150 µm [12], a 1 mm tip-height microneedle working electrode [85], and a high-density silicon microneedle patch containing approximately 9500 microneedles cm−2 [13]. A poly(methyl methacrylate) (PMMA) microneedle platform maintained structural integrity without swelling and allowed full skin recovery within 10 min after measurement [54]. PLA/functionalized multiwalled carbon nanotube (f-MWCNT) arrays with up to 6 wt% nanotube loading withstood axial forces up to four times higher than required for insertion [86].
These non-HFMN platforms show that robust insertion and dense electrode integration are achievable but do not resolve the central HFMN challenge: balancing pre-insertion mechanical strength with post-insertion swelling and diffusion. Additive manufacturing, air-spray coating, conductive-ink casting, and polymeric-lattice transfer expand the design space [37,87,88,89]. Laser-based patterning, laser-induced graphene processing, and mold-and-place assembly further broaden microneedle–electrode fabrication options [38,90,91,92]. Their HFMN relevance lies in structural lessons for miniaturization, surface area, electrode placement, and insertion reliability.

3.5. Diffusion Control, Antifouling Interfaces, and Mechanical Stabilization

For HFMN-enabled monitoring, the critical engineering problem is not only ISF access but also maintenance of a stable tissue–material–sensor interface during hydration, wear, and biological exposure. Protective and diffusion-regulating layers appear across microneedle classes. Water-soluble polymer coatings protected nanostructures during insertion and dissolved after ISF contact [93]. Polyurethane films reduced biofouling by large proteins and cells [94]. Nafion served as a diffusion-controlled membrane on planar polymer microneedles at 1.25 wt% [23], while double-layer fluorinated copolymer membranes used one layer to preserve enzyme activity and a second perfluorinated sulfonic acid layer as a diffusion-limiting barrier [24]. These examples support controlled diffusion as central to signal stability, but the evidence does not establish standardized criteria for matching membrane transport to relevant analyte ranges or long-term wear.
Mechanical stabilization further shows that insertion is a dynamic interface problem rather than a one-time event. Separated functionalization and assembly reduced coating damage in multichannel arrays [90]. Repeated insertion of a three-dimensional (3D)-printed solid microneedle sensor into porcine skin caused only an 8.4% signal decrease after four insertions [95]. Magnetic affixation prevented skin contraction from dislodging stereolithography-printed microneedle arrays in rodents [96]. A nanocavity-textured resilient bioelectrode supported 6 days of in vivo pharmacokinetic monitoring without structural degradation in stiff tissues [40]. These studies support designing HFMNs around insertion durability, adhesion, swelling control, and post-use tissue recovery rather than treating hydrogel formulation and sensing performance separately.

3.6. Decoupled Sampling Formats and Comparators Not Based on HFMNs

Several systems separate skin access from the final sensing event. Hydrogel microneedles coupled to graphene oxide–nucleic acid modules extracted ISF for in situ analysis [97], while a flexible HMN-based platform combined ISF-extracting hydrogel microneedles with flexible electrodes and used a separate HMN-based pH assay for concurrent pH tracking [28]. Micrometer-scale microneedles transferred microliter ISF volumes onto plasmonic paper [69], and macroporous-channel HMNs delivered ISF into paper-wick collectors [60]. These decoupled systems reduce the burden on the hydrogel or sampling matrix: the microneedle can focus on access and fluid handling while the sensor is optimized separately.
Comparator platforms should remain peripheral unless they clarify a transport or interface principle relevant to HFMNs. Saliva, sweat, plant-fluid, food, intracellular, nitrocellulose-membrane, and blood-plasma SERS and mass spectrometry systems demonstrate concepts in liquid transport, penetration mechanics, or direct tissue and matrix analysis but do not provide direct evidence for HFMN-mediated dermal ISF behavior [71,72,74,75,76,98,99]. The fish-tissue hypoxanthine example is best used only as a nonclinical demonstration of microneedle-enabled electrochemical sensing in a complex tissue matrix, not as evidence for HFMN-mediated ISF monitoring [77]. This distinction maintains the manuscript’s focus and avoids extending general microneedle-sensing findings to hydrogel-forming clinical platforms.

3.7. Architecture for Therapeutic Monitoring and Delivery

The transition from ISF biosensing to therapeutic monitoring is clearest when microneedles collect drug-containing ISF, support pharmacokinetic tracking, or connect sensing with controlled delivery. Several platforms demonstrate therapeutic drug monitoring without delivering therapy, including systems for antibiotics, fentanyl and analogues, non-redox-active molecular targets, and broader pharmacokinetic or drug-clearance assessment [6,28,29,39,40,70]. Related work, including phenylalanine tracking in human dermal ISF, further shows how microneedle access can support clinically interpretable monitoring beyond conventional metabolic sensing [27]. Thus, the architectural principles used for biomarker monitoring—swelling-hydrogel uptake, hollow-lumen sampling, capillary transport, diffusion barriers, and protected biointerfaces—can support therapeutic monitoring. However, they do not establish closed-loop therapy unless sensor output directly governs dosing or release.
Only a small subset explicitly demonstrates microneedle-mediated therapeutic delivery. A methotrexate platform paired a hollow microneedle monitoring patch with a separate iontophoretic HMN array containing both an anode and a cathode for on-demand transdermal methotrexate delivery [67]. Bilayer wound microneedles placed dissolvable polyvinylpyrrolidone antibiotic-loaded microneedles above conductive stainless-steel microneedles; after skin penetration, the polymer layer dissolved and released the drug into ISF, while the metallic component supported stimulation and sensing [41]. A biomimetic theranostic system used on-demand microneedle penetration to induce ISF exudation for epidermal analysis while enabling subcutaneous insulin delivery [42]. Thus, the evidence supports a strong trajectory from HFMN-enabled and broader microneedle ISF biosensing toward therapeutic monitoring, but true closed-loop drug delivery remains much less developed and should be described cautiously.
The architecture–transport patterns most relevant to sensing and therapeutic monitoring enabled by HFMNs are summarized in Table 2.

4. Molecular Recognition and Signal-Transduction Strategy

4.1. Recognition Chemistry at Hydrated Microneedle Interfaces

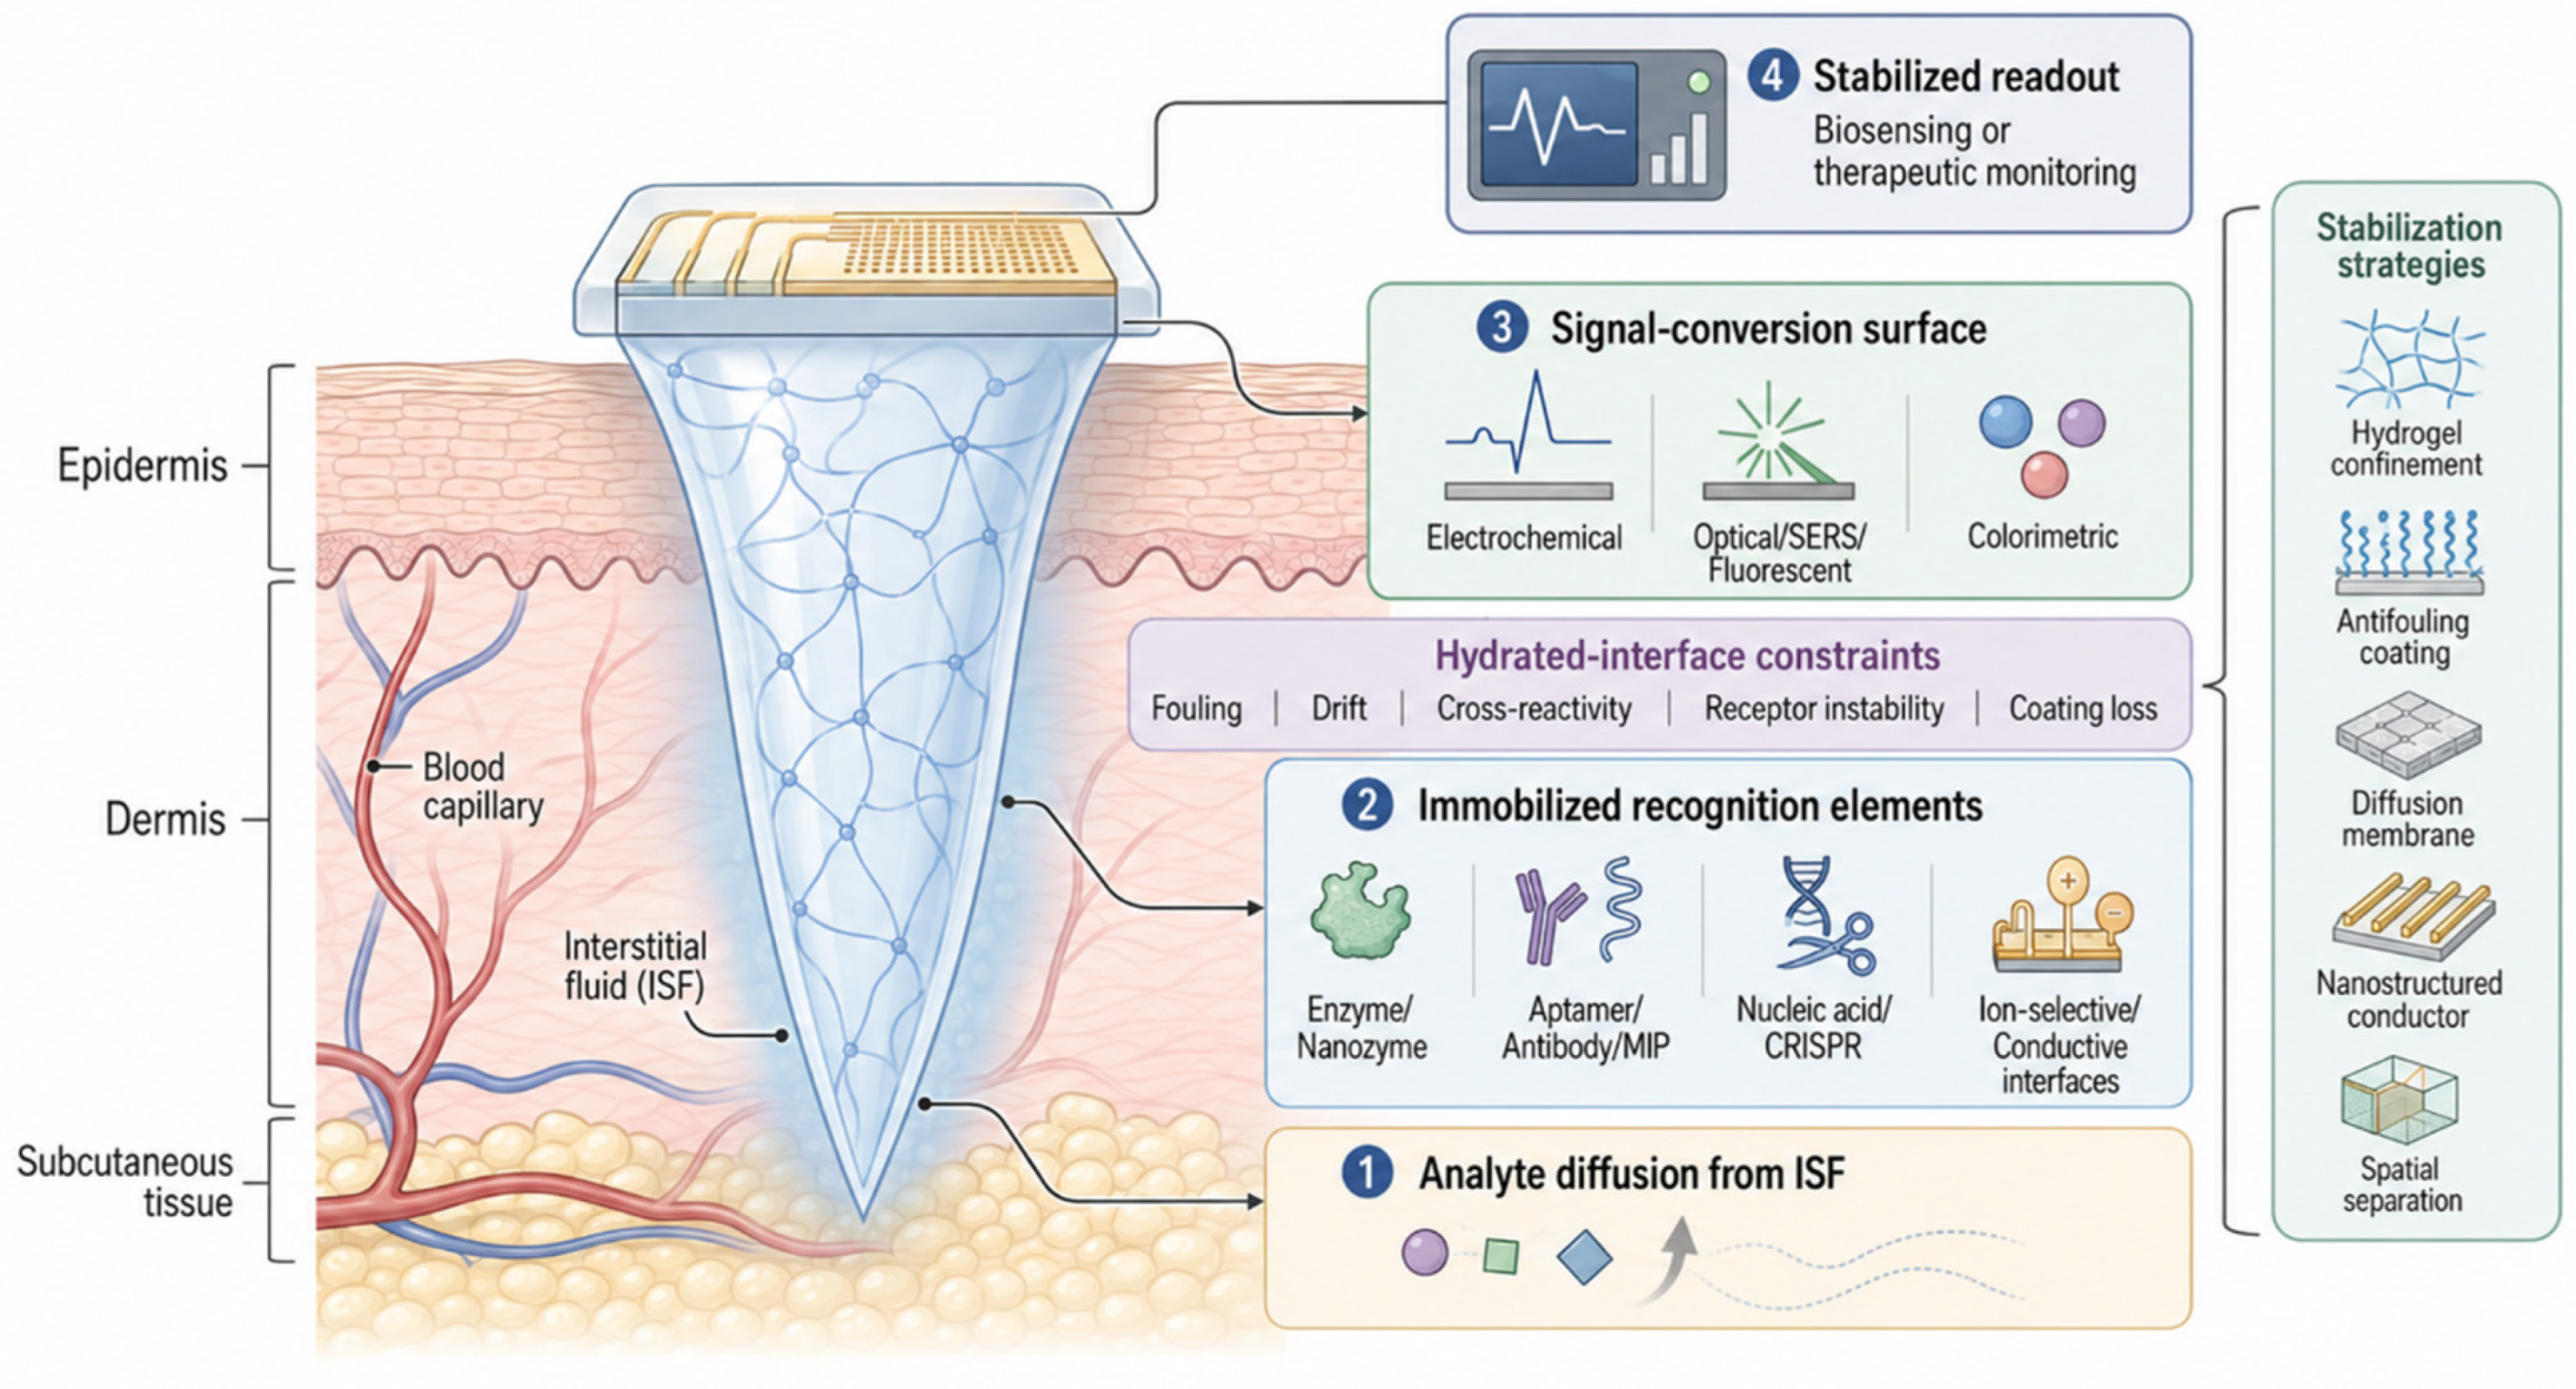
Molecular recognition in HFMNs and related hydrogel microneedle sensing systems have two linked requirements: the receptor must remain selective in a hydrated biological matrix, and recognition must be converted into a stable optical or electrical signal during ISF contact. Across the evidence base, the strongest mechanistic designs treat the hydrogel or porous microneedle not merely as a sampler but as an engineered microenvironment for receptor immobilization, analyte diffusion, antifouling protection, and signal transfer. This distinction matters because several reports demonstrate electrochemical, colorimetric, or optical sensing after microneedle-mediated sampling while emphasizing architecture, extraction, or transduction more than receptor-level recognition [11,13,84,87,100]. These studies support the feasibility of ISF-accessing transduction platforms but provide more limited mechanistic evidence for receptor-mediated selectivity.
Enzymatic sensing remains the most mature and consistently supported strategy for small-molecule metabolite monitoring. Glucose oxidase, flavin adenine dinucleotide-dependent glucose dehydrogenase, nicotinamide adenine dinucleotide-dependent glucose dehydrogenase, urease, lactate oxidase, and β-hydroxybutyrate dehydrogenase have been coupled to conductive supports, redox mediators, and protective membranes to convert catalytic turnover into amperometric or voltammetric signals [10,15,21,22,23,89,101]. Ketone-monitoring platforms extend enzymatic microneedle sensing toward diabetic ketoacidosis risk management, while peripheral enzymatic microneedle systems illustrate related analyte-specific sensing outside the central HFMN–ISF axis [19,77,101]. The collective evidence indicates that enzymatic microneedle sensors are no longer limited only by the availability of biological recognition elements; their performance is increasingly determined by interfacial engineering. Mediator layers, Prussian blue, ferrocene polymers, methylene blue, carbon nanotubes (CNTs), and gold/platinum- or reduced graphene oxide-based conductive supports regulate electron transfer and improve signal generation [15,21,85,89,91]. Nafion, polyurethane, o-phenylenediamine, hydrogel encapsulation, and fluorinated diffusion barriers reduce fouling, preserve enzyme activity, and suppress interference [22,23,24,94]. Low-potential operation, including −0.2 V and 0.15 V in glucose systems, can improve selectivity by limiting the oxidation of competing electroactive species [15,22]. However, the evidence does not establish long-term enzymatic stability under hydrated HFMN conditions, particularly during prolonged wear, wound-exudate exposure, repeated hydration–dehydration, or drug-delivery integration.
Nanozyme and nonenzymatic catalytic interfaces address some of the fragility of natural enzymes, but their selectivity requires cautious interpretation. Iron phthalocyanine–zeolitic imidazolate framework-8–MXene nanozymes, single-atom nanozymes, gold nanoparticle nanozymes, porous platinum black, gold/copper(I) oxide, and Prussian blue/CNT composites convert analyte-dependent reactions into electrochemical or colorimetric outputs [12,50,63,80,102]. These platforms show a clear movement toward replacing biologically labile enzymes with inorganic or hybrid catalysts that may better tolerate hydrated sensing environments. The strongest examples combine catalysis with interface-level design, including porous confinement, Nafion packaging, conductive MXene, or cascade colorimetry [12,80,102]. Still, catalytic activity should not be equated with molecular specificity unless interference testing and matrix stability are demonstrated. This distinction is especially important for HFMNs, where swelling, nonspecific adsorption, and local pH changes may alter the catalytic response.
Figure 3 summarizes the section’s central mechanistic logic: the hydrated microneedle interface must coordinate analyte diffusion, receptor immobilization, signal conversion, and stabilization before ISF biosensing can support reliable therapeutic monitoring.

4.2. Affinity-Based, Immunochemical, and Imprinted Recognition

Affinity-based recognition is the main mechanism moving microneedle sensing from conventional metabolite biosensing toward therapeutic and disease-state monitoring. Aptamers have been used for insulin, IgE, cortisol, phenylalanine, carcinoembryonic antigen, glucose/lactate, and endotoxin detection [16,25,26,27,56,64,66]. Related aptameric or aptamer-enabled hydrogel platforms support antibiotic monitoring, CRP tracking during resistant infection and vancomycin treatment, non-redox-active molecular sensing, and hybridization chain reaction-amplified cortisol detection [28,29,30,31,70]. Their value lies in extending ISF monitoring to drugs, hormones, proteins, and molecules without native enzymatic receptors. This class is mechanistically strongest when both immobilization and signal conversion are defined, including redox-tagged aptamer conformational changes, gold–thiol attachment on gold nanoparticle-functionalized microneedles, aptamer-triggered hybridization chain reaction fluorescence, or regenerable electrochemical aptamer arrays [26,31,56,70]. Dry-storage stability for phenylalanine aptamer sensors and porous microneedle immobilization of aptamer probes at 0.9459 µM on a 6.694 m2/g scaffold provide evidence that aptamer interfaces can be stabilized [27,66]. Nevertheless, literature does not resolve aptamer behavior under sustained swelling, local protein fouling, repeated mechanical deformation, or simultaneous drug-delivery exposure.
Immunochemical and protein-capture systems broaden analyte scope but add stability concerns. Human epidermal growth factor receptor 2 immunocapture on gold-coated silicon microneedles, antibody-based molecular pendulum sensors in zwitterionic hydrogels, CNT biointerfaces for cytokine markers, nanoporous microneedle immunoassays for S100 calcium-binding protein B, gold nanoparticle-based colorimetric detection of phosphorylated Tau 181, and microneedle electrochemical lateral-flow immunoassays for CRP show that microneedle formats can support protein-level recognition [18,32,33,34,35,98]. Most directly relevant to HFMNs, zwitterionic poly(carboxybetaine) hydrogel can protect antibody-based recognition elements during ultraviolet crosslinking and γ-irradiation [18]. This matters because many HFMN systems require hydrogel curing, sterilization, and hydrated storage conditions that may compromise proteins. However, protein recognition in hydrated matrices remains less mature than metabolite sensing, and evidence for antibody retention, antigen accessibility, nonspecific adsorption control, and continuous-use signal stability remains fragmented.
Molecularly imprinted polymers (MIPs) provide a synthetic alternative where enzymes, antibodies, or aptamers are unstable or costly. Examples include cortisol-imprinted polymers, analyte-imprinted layers for epinephrine, dopamine, and lactate, MIPs for interleukin-6, α-cyclodextrin-functionalized MIPs for dopamine, and a molecularly imprinted urea layer paired with a polyaniline pH sensor [55,73,74,103,104]. MIPs offer a plausible route to more robust recognition in hydrated microneedle devices, but the evidence should not be overread. Summaries support selectivity and repeated use in selected comparator systems, including reuse of a cortisol-imprinted sweat patch over 15 cycles across 30 days [73], but do not establish whether imprinted cavities retain affinity and selectivity after prolonged swelling, exposure to complex ISF proteins, or integration with drug-loaded hydrogel networks.
Nucleic acid- and CRISPR-enabled systems extend recognition to infectious, genetic, and prognostic biomarkers. CRISPR-associated protein 12a-enabled microneedles detect bacterial deoxyribonucleic acid (DNA) by cleaving ferrocene-labeled single-stranded DNA reporters, while CRISPR-activated graphene biointerfaces capture cell-free DNA and retain anti-interference capability in 60% fetal bovine serum with stable sensitivity over 10 days in vivo [53,65]. Probe DNA–graphene oxide conjugates and DNA-gated metal–organic frameworks enable fluorescence or dual fluorescence/SERS detection of microRNA targets [20,78]. Sequence-defined recognition is mechanistically compelling but imposes demanding requirements for probe retention, nuclease resistance, nonspecific matrix effects, and calibration in hydrated tissues. These systems are currently best viewed as promising HFMN-biosensing extensions rather than established therapeutic-monitoring tools.

4.3. Conductive, Ion-Selective, and Antifouling Transduction Layers

Conductive and nanostructured materials increasingly determine whether microneedle sensors remain usable during prolonged hydration and tissue contact. Vertical graphene, CNTs, laser-induced graphene, platinum/reduced graphene oxide, nanostructured gold, gold/copper(I) oxide, and metal–organic framework/CNT composites improve electron transfer, surface area, adsorption, and signal amplification [38,68,81,82,93,95,105]. Hydrogel-relevant and probe-based systems also incorporate MXene-containing materials, PEDOT:PSS, graphene oxide, and metal–organic framework components to support catalysis, conductivity, or signal transfer [5,8,9,20,97,102]. Conductive fillers are thus becoming central components rather than passive modifiers of the recognition–transduction interface. MXene contributes conductivity in iron phthalocyanine–zeolitic imidazolate framework-8–MXene nanozyme and antibacterial hydrogel wound platforms [8,102], PEDOT:PSS enables conductive hydrogel pH sensing and hydrogel microneedle working electrodes [5,8,9], and graphene oxide appears in conductive hydrogel electrodes and nucleic acid probe systems [8,9,20,97]. Comparative long-term cytocompatibility and skin-exposure profiles within hydrated hydrogel matrices remain less established. The studies support feasibility, conductivity, and selected biocompatibility or cytocompatibility claims but do not provide a unified basis for ranking PEDOT:PSS, graphene oxide, and MXene for extended skin or wound contact.
Biofouling, abrasion, coating delamination, and electrical drift threaten continuous microneedle sensing. Several studies address these limitations at the interface rather than solely through analytical chemistry. Recessed microcavities protect urea-sensing layers from delamination [83], water-soluble polymer shielding preserves platinum/reduced graphene oxide nanostructures until ISF contact [93], crosslinked chitosan reduces biofouling and promotes methotrexate adsorption [67], and dual-layer antimicrobial/antifouling architectures separate skin-contact functions from uric acid sensing [106]. Core–shell microneedles filled with zwitterionic hydrogel and an internal gold nanoconductive layer isolate the sensing region from subcutaneous friction [44], while resilient nanocavity-textured gold bioelectrodes extend pharmacokinetic monitoring by resisting abrasion in stiff tissues [40]. Magnetic placement of aptamer-functionalized microneedles further shows that stable electrical contact can be as important as receptor affinity for continuous molecular monitoring [96]. These studies collectively indicate that HFMN sensing accuracy depends on drift management, antifouling design, and mechanical protection of the sensing layer as much as on receptor selection.
Ion, pH, oxygen, and redox-state sensors provide physiological context for molecular signals. Polyaniline, iridium oxide, poly(3,4-ethylenedioxythiophene), electrolyte gels, gold-modified electrodes, and ion-selective or ion-monitoring interfaces have been used for pH, sodium ions, potassium ions, calcium ions, oxygen, and related ionic or redox-state measurements in skin, ISF, or subcutaneous settings [5,7,8,59,62,107,108]. Tungsten oxide and ferrocyanide redox couples illustrate useful peripheral designs for intracellular pH and food-matrix redox sensing but should remain comparator rather than central HFMN–ISF evidence [72,76]. Unlike receptor-driven biosensors, these systems often depend on potentiometric response, open-circuit voltage, redox potential, or conductive-polymer chemistry. They matter for HFMN-enabled therapeutic monitoring because drug response, wound state, inflammation, and tissue metabolism may be difficult to interpret from one molecular biomarker. However, local pH heterogeneity, biofilms, wound-exudate composition, and variable ionic strength may alter both contextual signals and adjacent biosensor performance. Reviewed wound and infected-wound platforms demonstrate multiplexed biochemical sensing and antimicrobial or electrically active components [8,41] but do not establish how complex wound microenvironments systematically affect selectivity, calibration, or drift.

4.4. Optical, Plasmonic, and Multimodal Signal Conversion

Optical and plasmonic microneedle sensors provide an alternative to electrode-dominated readouts, particularly for visual interpretation, molecular fingerprinting, or spatially separated multiplexing. Photonic aptamer-functionalized cholesteric liquid crystal networks detect illicit drugs through target-induced hydrogel contraction and photonic band-gap shifts [109]. SERS systems use silver coatings, Au@Ag core–satellite structures, self-assembled gold nanoparticle hot spots, plasmonic paper, gold nanorods, 4-mercaptophenylboronic acid chemistry, and gold nanoshells to detect glucose, uric acid, cholesterol, pH, drugs, bacteria, tyrosinase, and model compounds [39,46,54,69,110,111,112]. A plasmonic HMN patch integrates gold nanoparticles into a PEGDA hydrogel to support localized surface plasmon resonance and metal-enhanced fluorescence for biotin–streptavidin recognition [47]. These studies show that optical systems can convert binding, catalysis, probe displacement, bacterial capture, or Raman peak-ratio changes into measurable outputs without relying exclusively on electrochemical current.
The strongest optical designs pair recognition with a clear signal-generation mechanism. Examples include tyrosinase oxidation of immobilized dopamine, changing SERS probe density [110]; glucose oxidase-mediated conversion of 4-mercaptophenylboronic acid to 4-mercaptophenol, quantified by Raman peak ratios [113]; and spatially separated SERS zones for glucose, uric acid, and cholesterol using hydrophobic paraffin barriers [112]. Optical and SERS methods are particularly useful for multiplexing and molecular fingerprinting. Their limitations are also distinct: optical calibration, spectral overlap, nonspecific adsorption, hydration-dependent refractive changes, and probe stability may affect interpretation. These issues are especially relevant to HFMNs because swelling and analyte diffusion can change the optical path and local probe environment. The current evidence supports feasibility but does not yet define standardized calibration or drift-correction methods for prolonged hydrated wear.

4.5. Multiplexing and Transition Toward Therapeutic Monitoring

The field is moving from single-analyte ISF biosensing toward multiplexed platforms that could support therapeutic monitoring, although evidence strength varies by analyte class. Metabolite and metabolic-monitoring platforms, such as glucose/lactate, ketone-body monitoring, and glucose/uric acid/cholesterol, are mechanistically well supported where recognition chemistries are defined [16,19,21,112]. Aptamer-based or conductive electrochemical antibiotic- and drug-monitoring systems extend this concept to vancomycin, gentamicin, tobramycin, lidocaine, buprenorphine, olanzapine, fentanyl, and related therapeutic or toxicological targets [6,28,29,36,37,38]. Wound, inflammatory, and infectious-monitoring platforms integrate glucose, uric acid, pH, temperature, hydrogen peroxide, cytokines, cell-free DNA, and bacterial markers [8,34,41,46,65]. Collectively, these studies support connecting ISF biosensing to treatment monitoring through HFMNs. They do not uniformly demonstrate closed-loop therapy. Monitoring-only platforms should therefore be distinguished from systems integrating sensing with drug release, electrical stimulation, insulin delivery, or dose-relevant intervention [41,42,67].
Multiplexing introduces analytical risks not resolved by single-analyte performance metrics. Spatial separation, independent electrodes, hydrophobic barriers, parallel modules, and multimodal readouts can reduce crosstalk but cannot eliminate matrix effects, differential diffusion, local pH variation, protein fouling, or receptor incompatibility [8,16,28,55,90,112]. The most convincing systems explicitly separate recognition zones or combine orthogonal readouts; less detailed reports should be interpreted as platform demonstrations rather than validated multi-analyte measurement systems. Future performance sections should therefore evaluate multiplexed sensors by calibration stability, drift, biofouling resistance, wear duration, and post-use skin safety, as well as sensitivity and detection limit [1,2].
Table 3 summarizes the main mechanism-level priorities determining whether HFMN-compatible sensing interfaces can progress from ISF biosensing toward reliable therapeutic monitoring.
Overall, HFMN-compatible recognition and transduction strategies have advanced beyond simple ISF access. Enzymes and nanozymes support metabolite monitoring; aptamers, antibodies, MIPs, nucleic acid probes, and CRISPR systems extend detection to drugs, proteins, cytokines, nucleic acids, and pathogens; conductive and antifouling materials stabilize signal transfer; and optical methods add multiplexed or label-rich readouts. The central unresolved issue is whether the recognition interface can remain selective, calibrated, and mechanically stable during prolonged hydration, tissue contact, and, where relevant, therapeutic delivery—not whether microneedles can sample ISF or produce a signal. This criterion separates promising ISF biosensors from HFMN-based systems capable of reliable therapeutic monitoring.

5. Analytical Performance, Benchmarking, and Wear-Associated Failure Modes

5.1. Translational Meaning of Analytical Performance in HFMN Systems

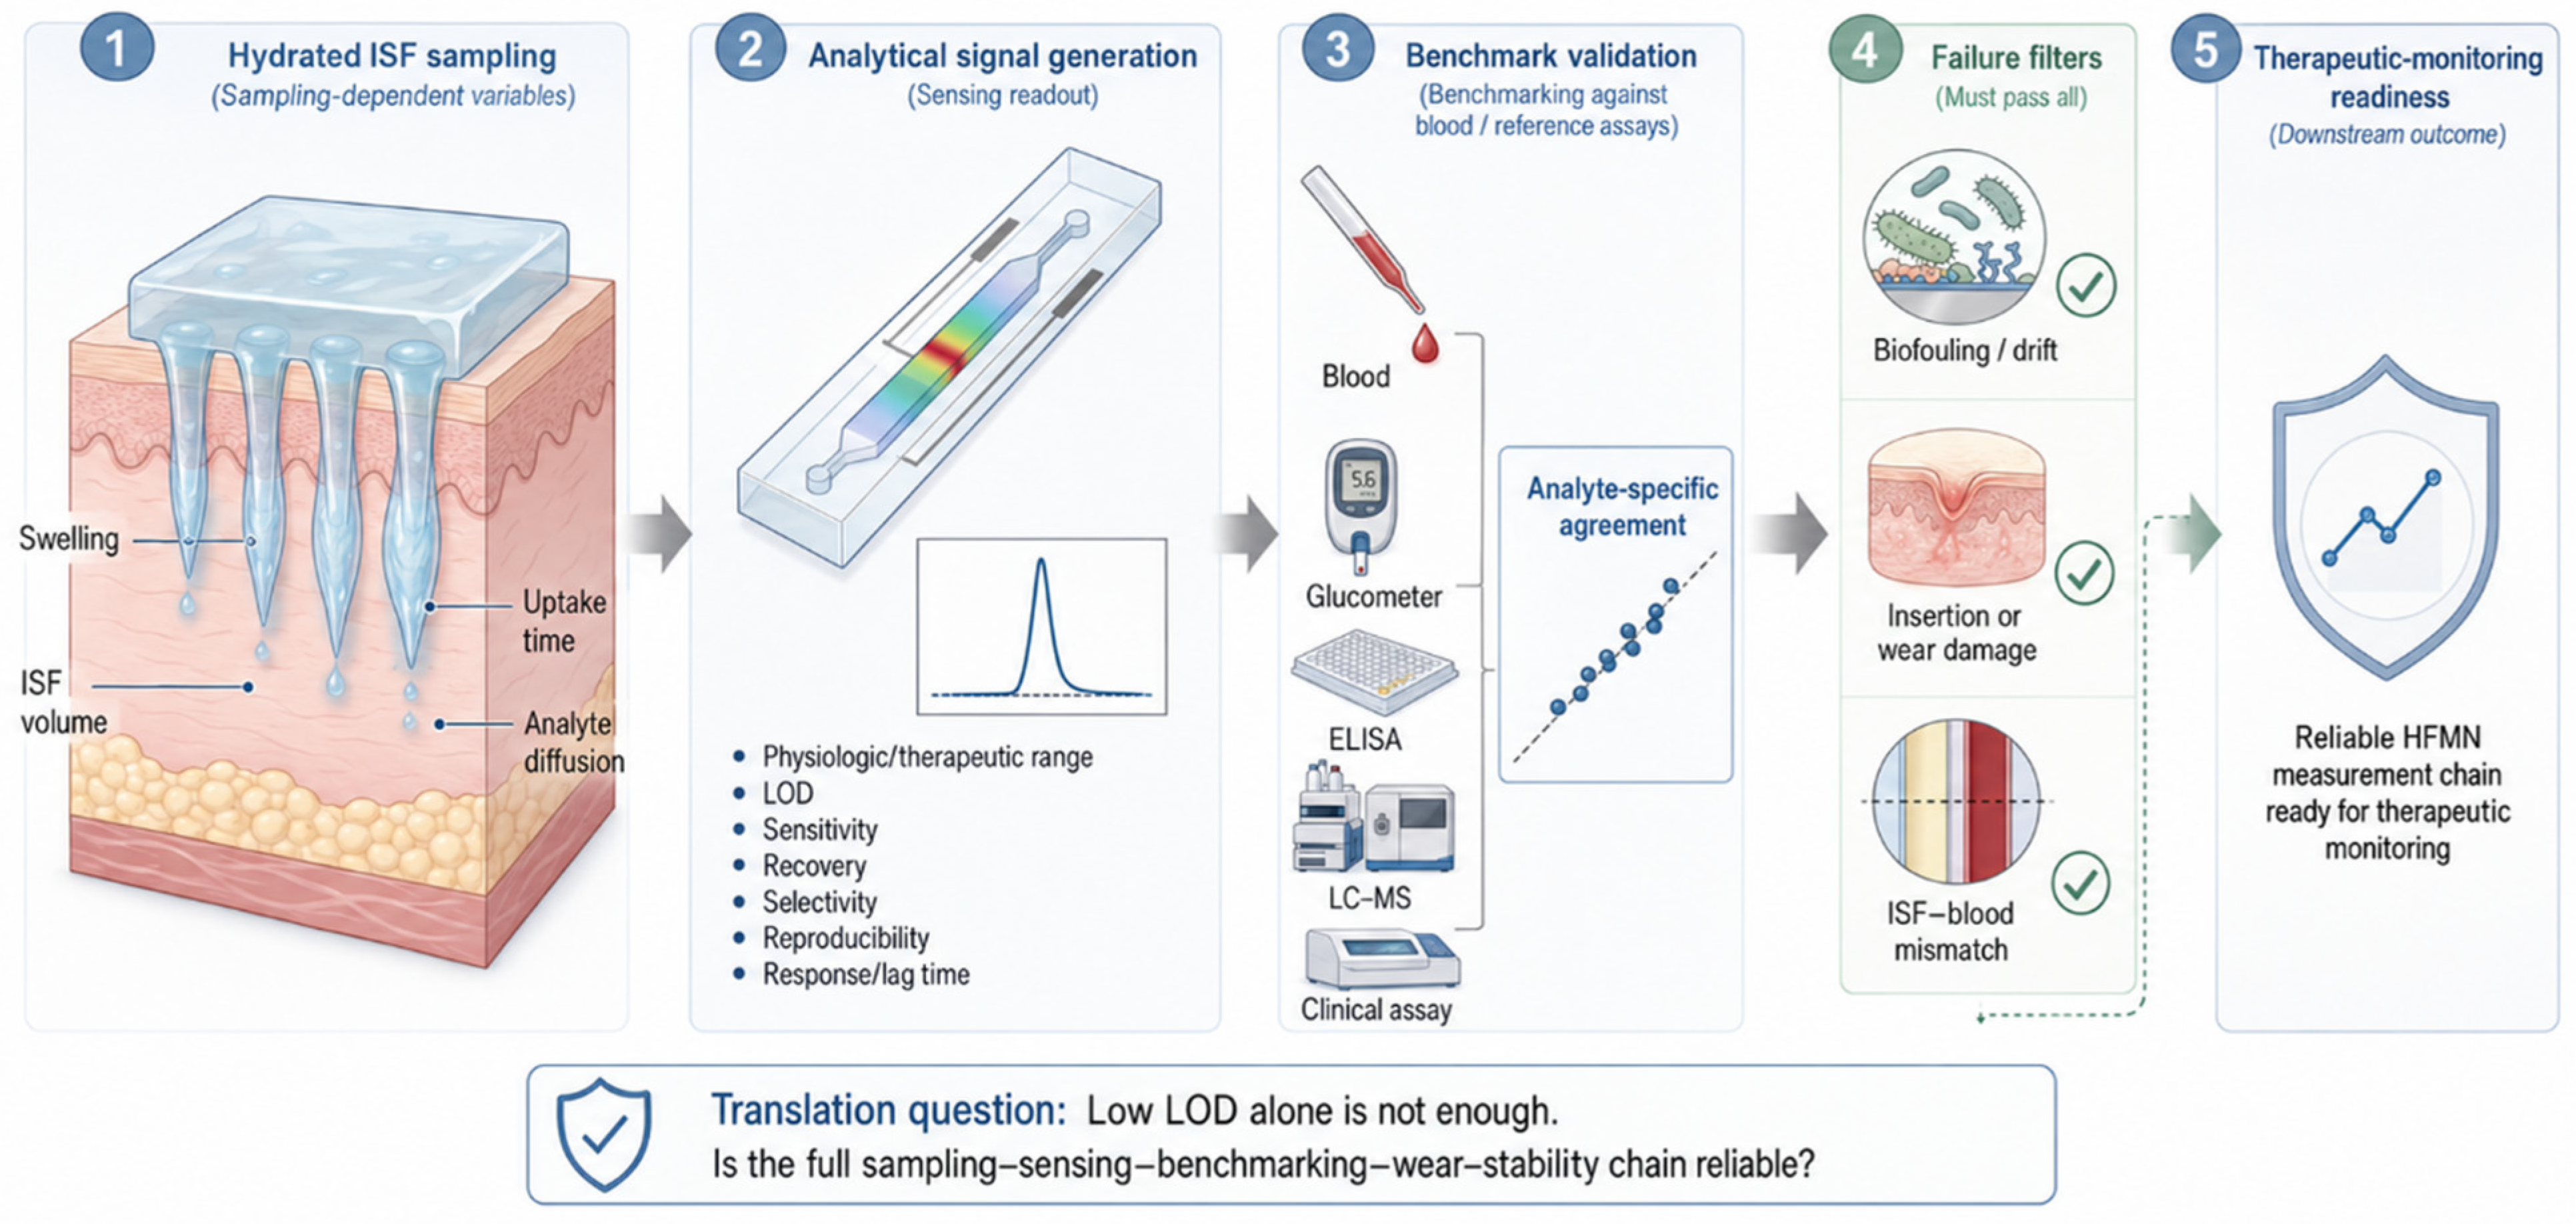
For HFMNs, analytical performance emerges from the coupled behavior of the hydrogel matrix, ISF extraction, analyte transport, sensor stability, and skin-contact mechanics rather than sensing chemistry alone. A low limit of detection is insufficient unless the sensor also covers physiologically or therapeutically meaningful concentrations, maintains calibration during hydration and wear, resists biofouling, and correlates with accepted comparators [1,2,43]. Glucose monitoring provides the most mature benchmark set, whereas therapeutic drugs, cytokines, nucleic acids, pathogens, and wound biomarkers are expanding rapidly but have less consistent validation [10,11,12,13,50,54,85]. Emerging platforms extend this evidence to therapeutic drugs, inflammatory or infectious markers, nucleic acids, bacterial targets, and wound biomarkers, but reporting remains uneven across analyte classes [8,28,29,46,65,78,115]. Several studies remain best treated as proof-of-concept or device-level demonstrations because summaries do not consistently report drift, calibration stability, wear duration, cross-reactivity, or post-use skin reliability [47,78,84,87,97,100,116]. This unevenness matters because HFMNs must function as hydrated, mechanically engaged sensing interfaces, not only sampling devices, if they are to inform therapeutic decisions.
Platform specificity is a second interpretive issue. Evidence includes true hydrogel-forming or hydrogel-assisted systems and porous, solid, metallic, polymeric, saliva-facing, sweat-facing, food-facing, plant-facing, or plasma-facing microneedles. These platforms are useful analytical comparators, particularly when quantifying drift, insertion loss, biofouling, or benchmark agreement, but their performance should not be generalized to dermal HFMNs without matrix- and wear-specific validation [12,52,71,72,75,79,99]. Figure 4 illustrates the central premise: analytical sensitivity becomes translationally meaningful only when the complete sampling–sensing–benchmarking–wear-stability chain remains reliable.

5.2. Metabolic Analytes and Physiological Ions

Glucose remains the clearest model for assessing whether HFMNs, hydrogel-relevant platforms, and comparator microneedle systems can progress from ISF biosensing to actionable monitoring. The strongest studies report clinically interpretable operating ranges, response kinetics, recovery, reproducibility, and comparator agreement rather than ultralow detection limits alone. Reported glucose ranges include 0.05–5 mM [21], 0.1–10 mM [117], 1–30 mM [12,15], 4–24 mM [85], 30–400 mg dL−1 [118], 0–20 mM [54,94], 0–30 mM [88], 1.0–40.0 mM in artificial ISF [22], linearity up to 35 mM [24], up to 14 mM [14], 1.5–14 mM [119], 0–15 mM [112,113], and 0.5–40 mM linearity within a broader 0.5–180 mM detection window [63]. The most complete profile combined a 1–30 mM dynamic range, 98.7–102% ISF recovery, sensitivities of 1.792 ± 0.25 µA mM−1 cm−2 in phosphate-buffered saline (PBS) and 0.957 ± 0.14 µA mM−1 cm−2 in ISF, detection limits of 7.2 µM and 22 µM, a 2 s response, intra- and interassay relative standard deviation (RSD) values of 1.64% and 0.70%, and only 3.5% signal loss over 16 days [12]. Complementary findings included an approximately 95 s in vivo response with a 0.357 µM detection limit [10], an approximately 2 min skin-model lag with 20% signal loss after 30 days [117], an approximately 3 s response with 7-day stability and strong glucometer correlation [15], and 28-day in vitro stability with correction of temperature-induced variation [24]. Human and reference-method comparisons included an approximately 10 min physiological delay relative to capillary blood [14], 93% of values in Clarke error grid zones A/B [54], and repeated correlation with commercial glucometers or blood glucose measurements [10,11,13,15,49,50].
For non-glucose metabolites, evidence is increasingly convincing when the reported range overlaps the relevant biological window. Lactate sensors achieved sensitivities of 797.4 ± 38.1 µA cm−2 mM−1 and 43.96 µA mM−1 cm−2, detection limits of 3 µM and 2.04 µM, a 10–100 µM range in one mediated system, linearity up to 10 mM in a planar polymeric microneedle system, and response times as fast as 8 s [21,23]. SERS microneedles resolved exercise-induced ISF lactate dynamics, including normal hindlimb increases from 2.41 ± 0.67 to 8.12 ± 1.05 mM after 3 min of swimming and to 13.85 ± 2.51 mM after 6 min [120]. Urea sensors reported detection limits of 0.1214 µM and 2.8 µM and ranges of 50–2500 µM, 0.1–15 mM, and 3–18 mM; the 3–18 mM range explicitly covered relevant physiological urea levels [4,83,89]. Uric acid platforms achieved detection limits as low as 20 nM and 0.17 µM, recovery of 98.6–100.4%, an RSD of 1.68%, enzyme-linked immunosorbent assay (ELISA) agreement, physiological-range detection, and broad linear ranges from micromolar to millimolar concentrations [61,81,95,105,106]. Ion and pH sensing further show why benchmark choice matters: pH systems reported −57.4 mV/pH over pH 4.0–9.0 [107], 93% accuracy against a conventional pH probe [5], −60.5 mV/pH with 97.7% accuracy and 2.3% error over 21 days [59], and stable intracellular pH monitoring across pH 6–11 with membrane-potential suppression as a contextual comparator [76]. A multiplex ion platform covered sodium ions from 0.75–200 mM, potassium ions from 1–128 mM, calcium ions from 0.25–4.25 mM, and pH from 5.5–8.5 while extracting approximately 6.87 µL per needle within 5 min [7]. Thus, analytical breadth is meaningful only with matrix relevance, stability, and interference control.

5.3. Neurochemical, Endocrine, and Therapeutic-Drug Monitoring

Neurochemical and endocrine monitoring extends HFMN-relevant and comparator microneedle sensing beyond metabolic analysis but increases the selectivity burden because structurally related and electroactive interferents are common. Dopamine detection reached a 0.58 nM limit over 5 nM–100 µM in buffer and 0.5–100 µM in artificial ISF [104], while another platform reported limits of 90 nM by square-wave voltammetry and 0.6 µM by chronoamperometry [114]. Total catecholamine sensing achieved a 100 nM detection limit in ISF-relevant testing [57]. Simultaneous uric acid/dopamine systems reported high sensitivities and ascorbic acid tolerance, supporting multiplexed detection where interference would otherwise be limiting [61,105]. Cortisol platforms illustrate the need to integrate sensitivity, range, matrix, and comparator agreement: benchmarks include 1–1000 nM with a 0.22 nM detection limit in simulated ISF [64], 0–100 ng/mL with a 1.4 ± 0.3 ng/mL detection limit and 15 reuses over 30 days in sweat [73], a 0.048 µM detection limit covering physiological ISF cortisol with ELISA agreement [31], and a 0.26 pg mL−1 detection limit with exercise-triggered sweat cortisol tracking and antimicrobial protection during wear [79].
Therapeutic-drug monitoring most directly connects biosensing with treatment adjustment but exposes a central limitation: ISF–blood relationships are analyte-specific. Hydrogel microneedle systems generated vancomycin and gentamicin pharmacokinetic profiles strongly correlated with conventional blood measurements [28], and aptamer-based patches showed strong ISF–blood correlation for tobramycin and vancomycin [29]. In contrast, a SERS comparison found comparable methylene blue concentrations in ISF and blood, whereas mitoxantrone levels were 2–3 orders of magnitude lower in ISF [39]. This difference cautions against treating ISF as a universal blood surrogate. Quantified drug sensors nevertheless show encouraging coverage: lidocaine over 1–120 µM with a 0.13 µM limit [36], buprenorphine over 2–140 µM with a 0.129 µM limit [37], olanzapine over 0.05–500 µM with a 0.0026 µM limit [38], MDMA over 1–50 µM with 0.05 µA µM−1 sensitivity and a 0.75 µM limit [68], methotrexate over 25–400 µM with more than 2 days of continuous operation and explicit suitability for high-dose therapeutic monitoring [67], and fentanyl over 10–100 µM with 0.3 µA µM−1 sensitivity and a 4.4 µM limit [6]. As a plasma-facing comparator rather than direct ISF evidence, SERS/substrate-supported electrospray ionization mass spectrometry (ssESI-MS) microneedles achieved subpicomolar fentanyl and alprazolam detection in plasma, a SERS enhancement factor of up to 1.0 × 10⁶, and successful identification in all 10 patient plasma samples [99]. For therapeutic monitoring, decisive evidence is sustained operation, therapeutic-window coverage, and validated interpretation of ISF concentrations relative to treatment-relevant comparators, not detection alone.

5.4. Protein, Nucleic-Acid, Pathogen, and Immune-Marker Assays

Macromolecular and pathogen sensing shows strong analytical ambition but uneven evidence for continuous monitoring. Immunoglobulin platforms reported an IgG detection limit of 0.05 ng mL−1 with 5.6 µL of ISF extraction in 5 min [17], and an IgE detection limit of 30.6 pg mL−1 across 88 pg mL−1–100 ng mL−1 with high specificity [26]. Cancer, neurological, and prognostic biomarker systems reported human epidermal growth factor receptor 2 detection over 10–250 ng mL−1 in artificial ISF with a 4.8 ng mL−1 limit and 50–250 ng mL−1 in phantom gel with a 25 ng mL−1 limit [32], carcinoembryonic antigen (CEA) detection over 0.05–500 ng mL−1 with limits of 0.012 ng mL−1 in PBS, 0.028 ng mL−1 in artificial ISF, and 0.034 ng mL−1 in a skin model [56], S100 calcium-binding protein B (S100B) detection at 20 pg mL−1 with high linearity and up to a 55% reduction in signal deviation [35], and phosphorylated Tau 181 (p-Tau181) detection at 16 pg mL−1 compared with 460 pg mL−1 on traditional two-dimensional (2D) surfaces [33]. Immune-marker sensors reported interleukin-6 (IL-6) detection as low as 1 pg mL−1 within 6 min [103], interferon-α (IFN-α) detection at 8.6 pg mL−1 with linearity up to 1000 pg mL−1 [115], and cytokine-storm marker detection at 0.54 pg mL−1 with 5-day stability, a 4.0% coefficient of variation, and a 1–4 h response to increasing cytokine levels [34].
Pathogen and nucleic acid platforms extend HFMN-compatible and microneedle-enabled monitoring toward infection and molecular diagnostics. A CRISPR-associated protein 12a (Cas12a) microneedle platform detected bacterial DNA at 0.69 pM ex situ and 6.3 pM in situ, with bacterial-load detection down to 4.27 × 10⁵ colony-forming units (CFU) mL−1 [53]. Hydrogel microneedles captured bacteria within 5 min with >50% efficiency, produced a linear SERS response from 1 × 10⁷ to 1 × 10¹⁰ CFU mL−1, and achieved 97.87% bacterial-identification accuracy [46]. Endotoxin detection covered 0.0342–8.2082 endotoxin units (EU) mL−1 with a 0.0064 EU mL−1 detection limit [66]. Cell-free DNA and microRNA (miRNA) systems reported anti-interference in 60% fetal bovine serum, stable in vivo sensitivity for 10 days, rapid ISF collection, high sequence specificity, and highly sensitive dual-mode detection, although complete numerical ranges or detection limits were not always provided [20,65,78]. Macromolecular platforms can therefore achieve impressive sensitivity, but fewer studies demonstrate the longitudinal calibration stability, fouling resistance, and repeated-use reliability required for therapeutic-response monitoring.

5.5. Sampling Reliability, Wear Stability, and Failure Modes

In HFMNs and related ISF-accessing microneedle systems, sampling cannot be separated from analytical performance. Extraction volume, swelling rate, capillary uptake, and transport delay determine whether the sensor receives a stable analyte supply. Reported metrics include vacuum pressures down to approximately −53 kPa and collection of approximately 2 µL of ISF per needle per hour [45], 5.6 µL within 5 min [17], 60.2 mg within 10 min [80], approximately 6.87 µL per needle within 5 min [7], and extraction yields/start-up times comparable to negative-pressure collectors with high paired-blood agreement for potassium, glucose, acetoacetate, and creatinine [60]. Reverse-iontophoresis-assisted sampling improved glucose extraction flux by approximately 1.6-fold [11]. These data establish swelling and fluid uptake as analytical variables because inconsistent extraction can cause calibration error, delayed response, or misleading blood agreement. Nonclinical microneedle studies, including plant-fluid extraction and fish-tissue hypoxanthine monitoring, further illustrate direct-sample benchmarking outside medicine [75,77]; the fish-tissue platform reported 5–50 and 50–200 µM hypoxanthine ranges, 0.024 µA µM−1 sensitivity, a 2.18 ± 0.75 µM detection limit, an approximately 100 s response, interference tolerance, and agreement with a commercial Amplex Red assay over 48 h [77]. Such studies are useful methodological comparators but should remain separate from dermal ISF claims.
Wear-associated failure modes are the evidence base’s most underdeveloped but clinically important component. Biofouling, delamination, abrasion, dehydration, motion, local inflammation, and loss of electrical contact can convert strong in vitro performance into unstable on-body data. Physical decoupling of ISF extraction from electrode transduction reduced abrasion-induced coating delamination and biofouling under identical insertion conditions [52]. Protective films limited fouling by large proteins and cells [94], chitosan coatings supported methotrexate sensing for more than 2 days [67], and antifouling/antimicrobial uric acid microneedles monitored mouse ISF without significant biofouling while matching ELISA [106]. Insertion-related damage was reduced through recessed microcavities protecting urea-sensing layers from delamination [83], polymer shielding of nanostructures for hydrogen peroxide (H2O2) sensing [93], separated functionalization to reduce coating damage and cross-interference [90], and structural viability during olanzapine sensing in penetration models [38]. Quantified insertion robustness remains uncommon; one nanostructured uric acid sensor showed only an 8.4% signal decrease after four porcine-skin insertions, <3.3% calibration difference during skin-piercing reversibility tests, and a 5.8% signal difference in preliminary on-body testing [95]. Magnetic affixation prevented rodent-skin contraction from pushing sensors out, preserved electrical contact, avoided irreversible array damage, enabled drift correction, and produced baseline drift rates comparable to those of successful in vivo aptamer sensors [96]. Longer-duration glucose and ion/pH evidence included 16-day glucose stability with 3.5% signal loss [12], 30-day glucose stability with 20% signal loss [117], 14-day repeatability with RSD < 4% [22], 21-day pH and 14-day sodium testing [59], 28-day in vitro glucose stability [24], and >14-day glucose service life [121]. Additional evidence included 90-day dry, room-temperature shelf storage for phenylalanine sensors [27], 10-day in vivo cell-free DNA sensitivity [65], and a 6-day in vivo lifetime for an abrasion-immune pharmacokinetic platform [40]. Prolonged monitoring is therefore feasible, but standardized wear studies are needed before stability claims can be compared across platforms.

5.6. Integrated Assessment

The evidence supports the premise that HFMNs and hydrogel-associated microneedle systems can extend ISF analysis from single-analyte biosensing toward therapeutic monitoring, but strength varies sharply by analyte class and validation depth. Glucose has the most mature analytical foundation, with many studies reporting physiologically relevant ranges, time response, stability, and comparator agreement. Small metabolites, ions, pH, and oxygen are also progressing toward clinically interpretable monitoring when ranges align with expected biological values. Therapeutic-drug monitoring is promising but more demanding because ISF concentrations require interpretation against analyte-specific blood or pharmacokinetic relationships. Macromolecular, nucleic-acid, pathogen, and immune-marker platforms show high sensitivity but often provide less evidence on drift, fouling, wear, and longitudinal calibration.
The conclusion is not that HFMN biosensors are uniformly ready for therapeutic monitoring, but that the field has identified the required performance criteria. The most convincing platforms combine physiologically or therapeutically matched ranges, matrix-specific calibration, response or lag-time characterization, recovery, reproducibility, selectivity, comparator agreement, and quantified resistance to biofouling, delamination, abrasion, drift, and insertion-related signal loss. Claims of monitoring–delivery integration should be reserved for systems in which sensor outputs demonstrably inform dosing, release, or treatment adjustment; monitoring-only platforms should be described as enabling technologies rather than closed-loop systems. Table 4 summarizes the analytical benchmarks and reliability criteria most relevant to HFMN-enabled ISF biosensing and therapeutic monitoring.

6. Validation Stage, Translational Readiness, and Closed-Loop or Drug-Delivery Implications

6.1. Translational Position of HFMN Biosensors

The validation landscape for HFMNs, hydrogel microneedles, HMNs, and closely related microneedle sensing platforms shows technical progress but incomplete clinical translation. Hydrogel-based systems combine minimally invasive skin interfacing with ISF uptake, localized sensing, and monitoring of metabolites, proteins, drugs, pH, nucleic acids, or wound biomarkers [5,6,8,18,20,28,78]. Selected hydrogel or hybrid microneedle platforms also provide antimicrobial, antifouling, stabilizing, or delivery-associated functions [8,41,44]. This trajectory supports the manuscript’s central premise of progression from ISF biosensing toward therapeutic monitoring. However, evidence remains stronger for feasibility and preclinical validation than for broad clinical implementation.
Many devices establish sensing feasibility in artificial ISF, buffers, hydrogel or skin phantoms, ex vivo tissue, serum, sweat, plant, food, plasma, or other simulated and peripheral matrices, but these models do not establish clinical readiness [22,32,36,47,77,99,109]. Animal studies provide a stronger translational bridge, particularly for glucose/lactate, proteins, antibiotics, wound biomarkers, delivery-associated wound therapy, nucleic acids, cytokines, pharmacokinetics, and organ-function monitoring [8,16,17,18,28,40,41]. Human evidence remains limited but important, including phenylalanine monitoring in human subjects, cortisol tracking in human volunteers, HMN-based glucose monitoring in the human forearm, hydrogel microneedle ketone monitoring in pilot human participants, and swellable microneedle ion extraction/detection in humans [7,14,19,27,64]. These studies mark meaningful progress but cannot define general clinical performance across analytes, skin types, wear durations, or patient populations.
Broader microneedle literature clarifies HFMN-relevant translational benchmarks, including comparator validation, wearability, sterilization, manufacturing, and monitoring–delivery integration. Nonclinical examples, such as direct electrochemical food-quality monitoring without sample preparation, indicate platform versatility rather than clinical maturity [77].

6.2. Comparator-Grounded Validation and Clinical Alignment

The most persuasive studies compare ISF readouts with accepted clinical or analytical methods. Glucose platforms have been aligned with commercial glucometers, capillary blood, or blood glucose trends in animal settings [10,11,13,15,16,50], and human forearm testing further defined physiological delay relative to capillary blood [14]. Urea monitoring was compared with the clinical glutamate dehydrogenase method [4], conductive hydrogel microneedle pH sensing achieved 93% in vivo accuracy relative to a conventional pH probe [5], and cortisol measurements were aligned with blood cortisol or ELISA, depending on the model [31,64]. Drug-monitoring studies provide particularly strong translational signals: antibiotic platforms correlated ISF drug measurements with blood-based values [28,29], CRP tracking during resistant infection and vancomycin treatment provided treatment-response context [30], model-drug pharmacokinetics were compared with liquid chromatography–mass spectrometry (LC–MS) blood measurements [39], and a resilient bioelectrode linked ISF pharmacokinetics to blood antibiotic profiles across kidney-disease severities while detecting delayed irinotecan clearance in liver-damaged models [40].
The critical lesson is that ISF cannot be treated as a universal blood substitute. The comparison of methylene blue and mitoxantrone pharmacokinetics is informative: one drug showed comparable ISF and blood concentrations, whereas the other was 2–3 orders of magnitude lower in ISF [39]. This finding cautions against extending single-analyte success to broader therapeutic-monitoring claims. Clinically actionable HFMN-enabled monitoring requires an analyte- or drug-class-specific correlation model, calibration strategy, and meaningful decision threshold.

6.3. Wearability, Safety, and Durability

Wearability has advanced through wireless readout, smartphone transmission, Bluetooth/smartphone connectivity, web-app visualization, automated alerts, artificial intelligence (AI)-assisted short-term forecasting, and self-powered operation. Smartphone-linked or wireless glucose systems include HMN and reverse-iontophoresis platforms, an emergency-alert glucose sensor, and a Bluetooth-enabled HMN glucose patch [11,58,119,121]. Web-app visualization and machine-learning-enabled drug readout support lidocaine and buprenorphine monitoring [36,37], while thermoelectric- or biofuel-cell-based microneedle systems support self-powered operation and AI-assisted short-term forecasting [48,85]. Several hydrogel or hydrogel-assisted systems also report operationally relevant sampling metrics, including rapid ISF extraction, capillarity-driven collection, and multi-analyte on-patch monitoring [7,28,60,80]. These features support wearable plausibility but not long-term clinical usability.
Evidence for durability and skin compatibility remains uneven. Studies report 14-day, 16-day, 21-day, 28-day, and more-than-14-day stability across sensing formats [12,22,24,59,121]. Others report 5–10-day in vivo sensitivity or 6-day pharmacokinetic monitoring in freely moving animals [34,40,65]. These data span different materials, analytes, and models, limiting direct comparison. Repeated insertion and post-use skin recovery are less developed. One PMMA SERS glucose microneedle reported complete skin recovery within 10 min [54], and one uric acid sensor showed limited signal loss after four porcine-skin insertions, small calibration changes, and preliminary on-body stability [95]. Other studies report cytocompatibility, biocompatibility, biosafety, antibacterial behavior, infection-risk suppression, or absence of significant tissue damage in ISF-facing and peripheral sweat-facing comparator platforms [8,20,41,44,79,115]. These findings support early safety feasibility but do not resolve repeated application, irritation, inflammation, barrier recovery, infection risk, or prolonged wear in intended users.

6.4. Manufacturing, Sterilization, and Quality Readiness

Practical manufacturing strategies include low-cost 3D printing, two-photon polymerization with soft lithography, direct casting, laser fabrication, mold-and-place assembly, clinical-grade needle conversion, secondary mold replication, film-like laser processing, micromolding, and molecularly imprinted systems with scalable potential. Additive and laser-enabled approaches include desktop resin printing, two-photon/direct-laser lithography with soft lithography, 3D-printed conducting microneedles, laser-induced graphene processing, and film-like laser-fabricated patches [37,38,58,87,92]. Molding, casting, conversion, and scalable comparator approaches include mold-and-place assembly, clinical-grade needle conversion, secondary mold replication, conductive-ink casting, micromolding from solvent-cast nanocomposites, and scalable recognition systems based on MIPs [29,86,89,91,103]. These approaches support translation but enable manufacturing processes rather than demonstrate regulatory readiness. Affordable fabrication does not demonstrate batch-to-batch reproducibility, validated release specifications, sterilization compatibility, or quality-controlled production.
Sterilization is among the least developed readiness domains. Only selected summaries directly address it: commercially available insulin-pen microneedles were described as sterilizable for vancomycin monitoring [116], and a zwitterionic hydrogel insulin patch preserved sensor function through ultraviolet (UV) crosslinking and Food and Drug Administration (FDA)-standard γ-irradiation [18]. This matters for HFMNs because sterilization may alter hydrogel swelling, mechanical strength, analyte transport, and biomolecular recognition. Isolated feasibility does not establish sterilization workflows across hydrogel chemistries, recognition elements, or integrated sensor formats. Review-level sources likewise identify material stability, signal drift, scalable manufacturing, closed-loop integration, and the absence of standardized testing as persistent translational barriers [1,2,3].

6.5. Therapeutic Monitoring, Drug Delivery, and Closed-Loop Status

The clearest advance is the shift from biosensing alone toward therapeutic monitoring. Drug- and treatment-relevant platforms have targeted vancomycin, gentamicin, tobramycin, lidocaine, buprenorphine, olanzapine, fentanyl, methylene blue, and mitoxantrone [6,28,29,36,37,38,39]. Additional support comes from methotrexate monitoring–delivery studies, regenerable aptamer-based monitoring of non-redox-active therapeutic targets, CRP tracking during methicillin-resistant Staphylococcus aureus (MRSA) infection and vancomycin therapy, and resilient pharmacokinetic monitoring across impaired organ-function models, including irinotecan clearance and antibiotic pharmacokinetics [30,40,67,70]. These studies support a feedback-informed model in which ISF data may characterize exposure, toxicity risk, treatment response, or dosing windows. Related systems include AI-assisted 20-min biomarker forecasting, abnormal-glucose alerts, machine-learning drug-level visualization, CRP tracking during MRSA infection and vancomycin therapy, and pharmacokinetic monitoring intended to support precision dosing [30,36,37,40,48,119].
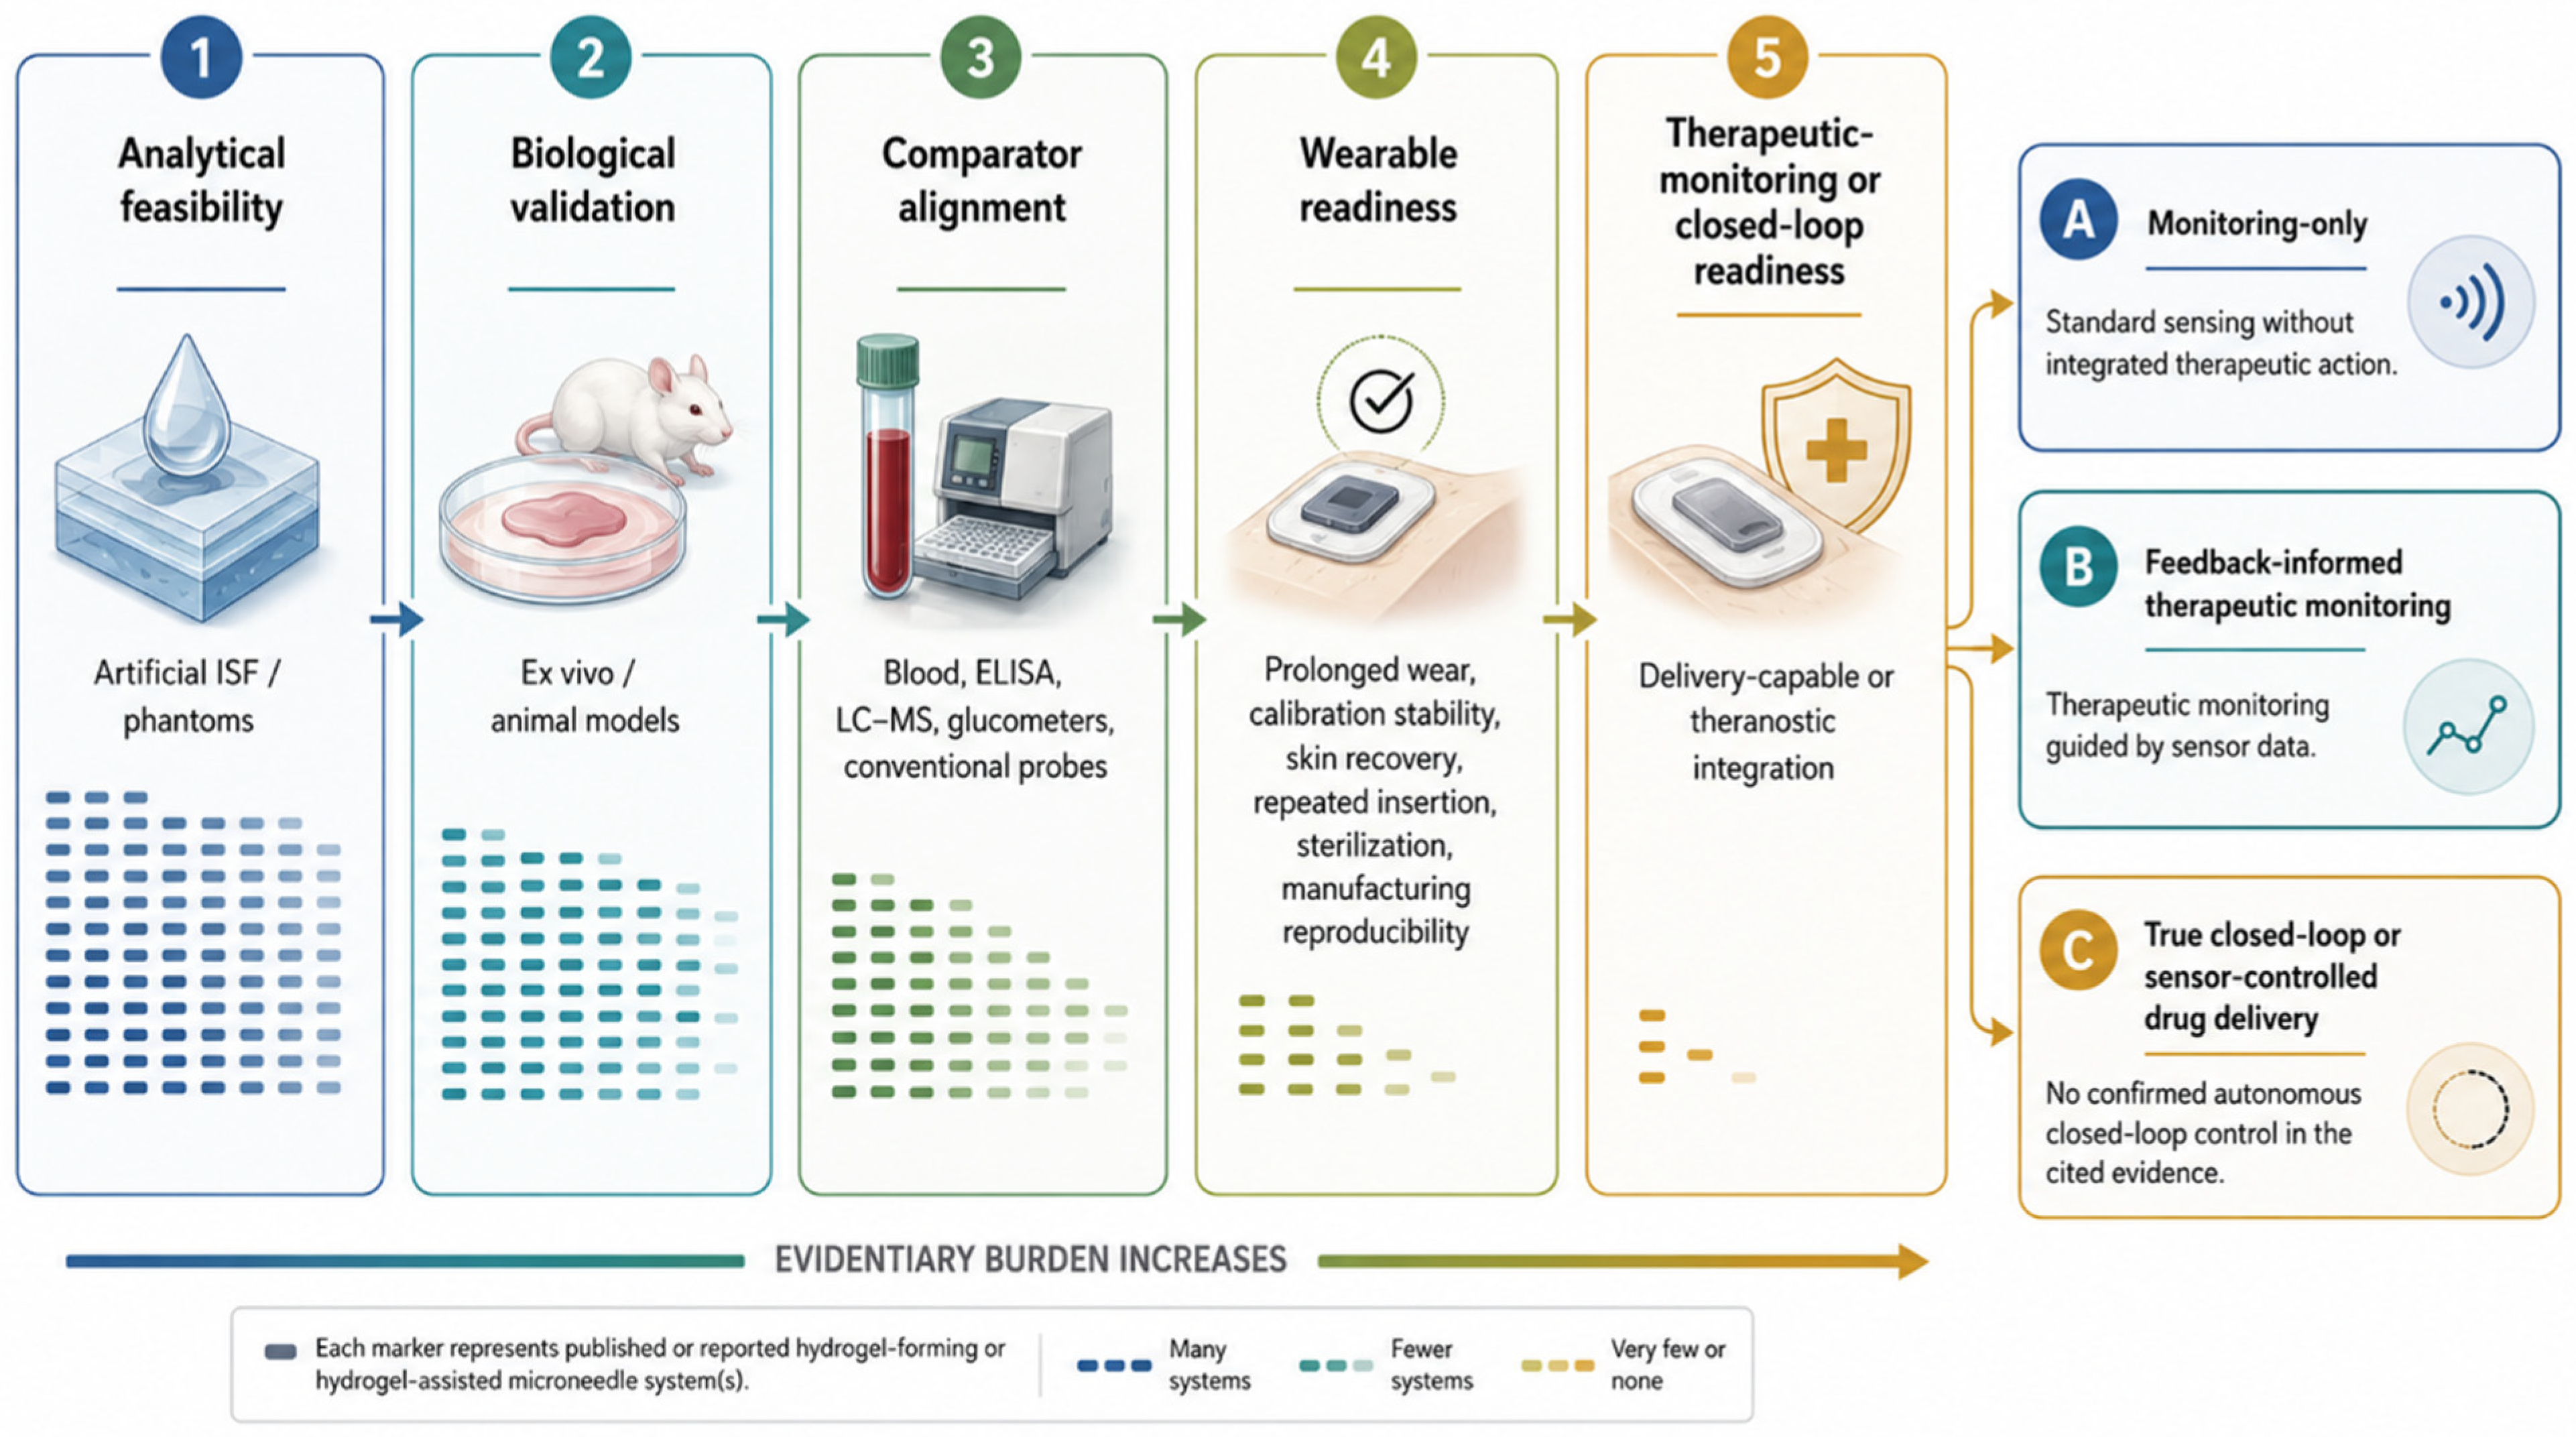
This evidence requires careful framing. Most platforms remain monitoring-only, detecting biomarkers, drugs, ions, pathogens, cytokines, nucleic acids, wound states, metabolic markers, or nonclinical quality markers without directly controlling a therapeutic actuator. A smaller subset is theranostic or delivery capable. The methotrexate system combined continuous sensing with a separate iontophoretic delivery patch and sustained operation for more than 2 days in vitro and ex vivo [67]. An HFMN wound dressing monitored seven wound biomarkers, demonstrated cytocompatibility and antimicrobial effects, and accelerated wound closure in rats [8]. A microneedle–triboelectric nanogenerator (MN-TENG) platform combined antibiotic release, electrical stimulation, and biomarker monitoring in animal wound models [41]. A biomimetic diabetic platform combined glucose/ion detection with subcutaneous insulin delivery and hyperglycemia regulation [42]. These systems approach treatment, but the cited evidence does not demonstrate autonomous sensor-output-controlled drug release, dose adjustment, or actuator regulation. They should therefore be described as theranostic, delivery-capable, or feedback-capable, not as confirmed closed-loop systems. Figure 5 illustrates this evidence-gate structure, and Table 5 summarizes the corresponding validation patterns.

6.6. Translational Gaps and Implications

Beyond simple ISF sampling, the field includes wearable biosensing, multiplexed monitoring, treatment-response assessment, pharmacokinetic profiling, and selected theranostic functions [8,28,30,40,41,42]. HFMNs and hydrogel-enabled microneedle platforms are central to this progression because their hydrated networks support ISF uptake, conformal skin interfacing, and integration with sensing or treatment-associated components [5,6,8,18,20,28,78]. HMNs and other non-hydrogel microneedle formats remain important comparators when they clarify sampling, transport, or validation benchmarks. Yet, the evidence supports feasibility and preclinical promises more strongly than clinical implementation.
Several gaps are defining translational barriers, not routine future work. First, validation pathways remain inconsistent; progression from artificial ISF to ex vivo skin, animal models, and human testing lack shared acceptance criteria. Second, skin models are not interchangeable: rodent, porcine, and human skin differ in insertion behavior, barrier properties, ISF accessibility, and hydrogel swelling context, so successful preclinical insertion cannot be assumed to predict human use. Third, prolonged wear introduces unresolved risks of biofouling, signal drift, enzyme or aptamer instability, hydrogel dehydration or overswelling, local pH variability, irritation, inflammation, and infection. Fourth, integrated sensors may alter microneedle mechanical integrity, insertion strength, swelling behavior, analyte diffusion, and drug-release kinetics; these interactions are not consistently quantified [1,2,3,43]. Finally, regulatory translation will require sterilization validation, storage stability, manufacturing reproducibility, quality-controlled production parameters, and clinically meaningful endpoints such as dosing accuracy, toxicity reduction, infection control, wound closure, glycemic or ketoacidosis management, and improved treatment response [1,2,8,19,41,42,67].

7. Limitations and Future Perspectives

Despite rapid progress, evidence remains uneven across materials, analytes, validation models, and translational endpoints. A major limitation is inconsistent reporting of HFMN structure–function relationships. Many studies report swelling, insertion force, uptake volume, or response kinetics, but few connect these metrics with network chemistry, crosslinking density, analyte diffusion, receptor retention, and post-insertion integrity within one platform. This limits comparison across PEGDA, MeHA, hyaluronic acid derivatives, PVA/chitosan composites, zwitterionic hydrogels, and conductive hydrogel matrices [4,5,6,7,8,18,44]. GelMA, hyaluronic acid/sodium hyaluronate, MeHA–probe, and DNA-gated hydrogel systems broaden the material landscape but do not resolve this structure–function gap [20,30,31,78]. Future studies should report a minimum dataset including needle geometry, insertion force, swelling ratio, ISF uptake kinetics, diffusion characteristics, skin recovery, and sensor performance before and after insertion.
A second limitation is the frequent separation of sensing performance from real wear conditions. Many platforms achieve excellent limits of detection (LODs), dynamic ranges, or response times in artificial ISF, buffers, phantoms, serum, plasma, or ex vivo tissues, but these conditions do not reproduce the mechanical, biochemical, and immunological complexity of hydrated skin contact [6,12,22,32,36,56,89]. Photonic, pathogen, plasma-facing, and SERS systems reinforce this feasibility pattern but remain short of clinical wear validation [46,99,109,112,113]. Prolonged wear introduces biofouling, coating delamination, receptor degradation, hydration-induced drift, motion artifacts, skin inflammation, and changes in local ISF flux. Decoupled porous sampling designs, protected microcavities, core–shell structures, zwitterionic hydrogels, Nafion or polyurethane barriers, and antifouling conductive interfaces offer partial solutions [18,22,44,52,83,95], but no dominant engineering strategy has emerged. Long-duration studies under motion, perspiration, temperature variation, repeated application, and clinically relevant skin conditions should be prioritized.
Analytical validation also remains analyte-specific. Glucose has the strongest benchmark ecosystem, with repeated comparisons to commercial glucometers, capillary blood, or blood glucose trends [10,11,13,14,15,49,50]. Other analytes, including cortisol, urea, pH, ions, antibiotics, and drug-clearance markers, have begun to show clinically meaningful comparator alignment [4,5,28,29,31,40,64]. However, ISF–blood relationships cannot be generalized across molecules. Pharmacokinetic studies showing divergent ISF and blood behavior for different drugs highlight the risk of assuming universal equivalence between compartments [39]. Future therapeutic-monitoring work should define analyte-specific correlation models, lag times, calibration strategies, actionable thresholds, and conditions under which ISF measurements diverge from blood-based interpretation.
Recognition chemistry presents another translational bottleneck. Enzymatic sensors are mature but vulnerable to denaturation, oxygen dependence, mediator instability, and activity loss during prolonged hydration or sterilization [15,21,22,24]. Aptamers broaden the accessible analyte space and support real-time molecular monitoring, but their behavior under sustained swelling, nucleolytic exposure, nonspecific adsorption, and repeated mechanical deformation remains incompletely characterized [27,28,29,30,31,64,70]. Immunochemical systems are promising for proteins but raise concerns regarding antibody orientation, antigen accessibility, hydrogel curing, γ-sterilization, and long-term storage [18,32,33,34,35]. MIPs, nanozymes, CRISPR-enabled systems, and DNA-gated materials offer attractive alternatives, yet each requires rigorous testing in complex ISF and under prolonged skin-contact conditions [12,20,65,78,80,102,103]. Future HFMN platforms should treat receptor stability as a central design parameter, not a secondary analytical feature.
Manufacturing and sterilization lag behind sensing innovation. Additive manufacturing, laser processing, two-photon polymerization, mold-and-place assembly, commercial needle conversion, micromolding, and scalable MIP systems have improved fabrication feasibility [29,37,38,58,87,91,103]. Casting and nanocomposite-based strategies expand process options [86,89,92]. Nevertheless, scalable production requires batch-to-batch reproducibility, release specifications, dimensional tolerances, mechanical quality control, shelf-life testing, packaging compatibility, and validated sterilization. Sterilization is particularly challenging for HFMNs because it may alter hydrogel swelling, mechanical behavior, conductivity, receptor activity, and analyte transport. Preservation of antibody-based sensor function through UV crosslinking and γ-irradiation is encouraging [18], and sterilizable commercial off-the-shelf (COTS) microneedles provide a useful comparator signal [116], but isolated success does not establish platform-wide readiness. Future studies should integrate sterilization and shelflife testing early in development.
Human validation remains sparse. Human-facing studies, including continuous phenylalanine monitoring, cortisol tracking, HMN glucose monitoring, ketone monitoring, and swellable microneedle ion detection, show that ISF microneedle sensing can move beyond animal models [7,14,19,27,64]. However, these studies remain insufficient to define performance across age, sex, skin pigmentation, dermatologic status, hydration state, disease severity, medication exposure, and long-term use. Prospective clinical studies should evaluate analytical accuracy, usability, comfort, adherence, adverse skin events, failure rates, data interpretability, and impact on clinical decisions.
Finally, closed-loop and therapeutic integration should be framed carefully. The field has produced important prototypes linking sensing with drug delivery, antimicrobial action, electrical stimulation, wound management, or insulin administration [8,41,42,67]. However, most HFMN and hydrogel-relevant systems still generate information rather than autonomously modifying therapy. Future closed-loop platforms will require validated control algorithms, fail-safe mechanisms, dose-delivery accuracy, biocompatible actuation, regulatory-grade risk analysis, and evidence that feedback improves outcomes compared with monitoring alone. The most realistic near-term path may be decision-support systems for therapeutic drug monitoring, infection management, metabolic instability, and wound care, followed by progressively more autonomous feedback-controlled platforms as safety and interpretability improve.

8. Conclusions

Hydrogel-forming microneedles have advanced from minimally invasive sampling structures into multifunctional biointerfaces capable of accessing interstitial fluid, stabilizing hydrated sensing environments, and supporting diverse biochemical readouts. Their defining strength is integrating skin penetration, fluid uptake, analyte transport, and sensor compatibility within soft polymeric architectures. This positions them between conventional wearable sensors and invasive clinical sampling.
The field now extends well beyond glucose monitoring. HFMN and hydrogel-relevant systems have demonstrated detection of metabolites, ions, hormones, proteins, nucleic acids, infection markers, wound biomarkers, and therapeutic drugs. These advances support a compelling vision of continuous, personalized, feedback-informed healthcare. However, the evidence does not yet justify broad claims of mature closed-loop therapy or universal substitution for blood-based testing. Translation will require standardized benchmarking, analyte-specific validation, long-wear reliability, sterilization-compatible materials, scalable manufacturing, and clinically meaningful interpretation of ISF signals.
The next phase should prioritize integration over novelty. HFMNs will achieve their greatest impact when material design, recognition chemistry, transduction stability, skin compatibility, data interpretation, and therapeutic decision-making are developed as a single system. If these challenges are met, hydrogel-forming microneedles could become a foundational platform for minimally invasive biochemical monitoring and precision therapeutic management.

9. Evidence-to-Practice Roadmap

This roadmap (Table 6) translates the reviewed evidence into practice-facing priorities without reclassifying device types, repeating sensing mechanisms, or duplicating validation-stage summaries. It preserves the manuscript’s central argument: hydrogel-forming and hydrogel-integrated microneedles provide a strong foundation for minimally invasive interstitial-fluid biosensing and therapeutic monitoring, but responsible clinical translation requires analyte-specific validation, measurable clinical benefit, manufacturable device quality, and cautious framing of closed-loop claims.

Author Contributions

The authors confirm contributions to the paper as follows: conceptualization, writing, review, and editing, H.O.; investigation, review, and editing, S.D.C. All authors have read and agreed to the published version of the manuscript.

Funding

This review article received no external funding.

Data Availability Statement

No new data were created or analyzed in this study. Data sharing is not applicable to this article.

Acknowledgments

Non-AI research and reference-management tools, including the Web of Science and EndNote, were used to support literature searching, citation organization, and reference management. AI-assisted tools, including OpenAI ChatGPT Plus 5.5, Gemini Pro 3.6, and NotebookLM were also used during manuscript preparation to support literature analysis, improve clarity and organization, enhance accuracy, and assist in the conceptual development and refinement of figures. These tools were used solely as supportive aids. Any AI-assisted figures are conceptual illustrations and do not represent raw experimental data, clinical images, microscopy images, diagnostic materials, or manipulated research outputs. No third-party copyrighted or proprietary images were intentionally uploaded, copied, reproduced, or incorporated. To the best of the authors’ knowledge, the final figures are original conceptual illustrations prepared for this manuscript. The authors reviewed, edited, verified, and finalized all AI-assisted text and figure content.

Conflicts of Interest

The authors declare no conflict of interest.

Abbreviations

2D two-dimensional
3D three-dimensional
AI artificial intelligence
Au@Aggold–silver core–shell
Cas12a CRISPR-associated protein 12a
CEA carcinoembryonic antigen
CFU colony-forming units
CNTs carbon nanotubes
COTS commercial off-the-shelf
CRISPR clustered regularly interspaced short palindromic repeats
CRP C-reactive protein
DNA deoxyribonucleic acid
ELISA enzyme-linked immunosorbent assay
ETPTA ethoxylated trimethylolpropane triacrylate
EU endotoxin units
f-MWCNT functionalized multi-walled carbon nanotube
FDA Food and Drug Administration
GelMA gelatin methacryloyl
HA-MAhyaluronic acid methacryloyl
H2O2hydrogen peroxide
HFMNs hydrogel-forming microneedles
HMNs hollow microneedles
IFN-αinterferon-alpha
IgE immunoglobulin E
IgG immunoglobulin G
IL-6interleukin-6
ISF interstitial fluid
LC–MSliquid chromatography–mass spectrometry
LOD limit of detection
LSPR localized surface plasmon resonance
MDMA 3,4-methylenedioxymethamphetamine
MEF metal-enhanced fluorescence
MeHA methacrylated hyaluronic acid
MgCl2 magnesium chloride
miRNA microRNA
MIPs molecularly imprinted polymers
MN-TENGmicroneedle–triboelectric nanogenerator
MNTP microneedle theranostic platform
MOFs metal–organic frameworks
MRSA methicillin-resistant Staphylococcus aureus
PBS phosphate-buffered saline
PEDOT:PSS poly(3,4-ethylenedioxythiophene):poly(styrenesulfonate)
PEG poly(ethylene glycol)
PEGDA poly(ethylene glycol) diacrylate
pH potential of hydrogen
PLA poly(lactic acid)
PMMA poly(methyl methacrylate)
p-Tau181 phosphorylated Tau 181
PVA poly(vinyl alcohol)
PVP polyvinylpyrrolidone
RSD relative standard deviation
S100B S100 calcium-binding protein B
SERS surface-enhanced Raman scattering
ssESI-MSsubstrate-supported electrospray ionization mass spectrometry
TDM therapeutic drug monitoring
uSMART integrated ultraswelling microneedle aptamer-recognition tester
UV ultraviolet
μNEAB microneedle-based electrochemical aptamer biosensing

References

  1. Cho, J.; Son, H.; Kim, J.; Song, H.S.; Lee, W. Wearable microneedle sensors for continuous interstitial fluid monitoring. Biosens. Bioelectron. 2026, 297, 118385. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  2. Gong, X.X.; Wen, Y.R.; Pang, Y.M.; Liu, S.; Yuan, Q. Progress of Microneedle Electrochemical Biosensors for Interstitial Fluid Detection and Monitoring. Chin. J. Chem. 2025, 43, 3016–3032. [Google Scholar] [CrossRef] [Scilit]
  3. Zhou, L.; Liang, N.; Zheng, Y.; Sun, X.; He, J.; Huang, B. Integration of hydrogel microneedle with advanced sensing technologies: From biomarker detection to clinical applications. Appl. Mater. Today 2025, 46, 102869. [Google Scholar] [CrossRef] [Scilit]
  4. Basumatary, I.; Chauhan, S.S.; Venuganti, V.V.K.; Sahatiya, P. Microneedle array integrated 2D NiSe2/MXene-based real-time urea sensing in interstitial fluid. Electrochim. Acta 2025, 528, 146299. [Google Scholar] [CrossRef] [Scilit]
  5. Odinotski, S.; Dhingra, K.; GhavamiNejad, A.; Zheng, H.J.; GhavamiNejad, P.; Gaouda, H.; Mohammadrezaei, D.; Poudineh, M. A Conductive Hydrogel-Based Microneedle Platform for Real-Time pH Measurement in Live Animals. Small 2022, 18, 2200201. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Wu, T.H.; Huang, Q.Z.; Luo, J.X.; Li, J.C.; Wang, Y.; Lin, S.Y.; Li, Z.H.; Liu, W.B.; Wang, Z.F.; Zhao, X.J.; et al. A flexible hydrogel microneedle patch-mediated electrochemical sensor for rapid and minimally invasive fentanyl detection. Talanta 2026, 306, 129708. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Zhu, D.D.; Tan, Y.R.; Zheng, L.W.; Lao, J.Z.; Liu, J.Y.; Yu, J.; Chen, P. Microneedle-Coupled Epidermal Sensors for In-Situ-Multiplexed Ion Detection in Interstitial Fluids. ACS Appl. Mater. Interfaces 2023, 15, 14146–14154. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Sharifuzzaman, M.; Hasabnis, G.; Abu Saleh, S.A.; Siebert, L.; Hövener, J.B.; Maschkowitz, G.; Altintas, Z. Hydrogel Microneedle Array-Based Transdermal Dressing System for Multiplexed Assessment and Intelligent Therapy of Chronic Wounds. Small 2026, 22, e11542. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  9. Shirzadi, E.; Huynh, M.; GhavamiNejad, P.; Zheng, H.J.; Saini, A.; Bakhshandeh, F.; Keyvani, F.; Mantaila, D.; Rahman, F.A.; Quadrilatero, J.; et al. A PEDOT:PSS-Based Composite Hydrogel as a Versatile Electrode for Wearable Microneedle Sensing Platforms. Adv. Sens. Res. 2024, 3, 2300122. [Google Scholar] [CrossRef] [Scilit]
  10. Basumatary, I.; Chauhan, S.S.; Venuganti, V.V.K.; Sahatiya, P. Microneedle-assisted interstitial fluid extraction combined with a 2D tellurene-based glucose sensor for personal diabetes management. J. Mater. Chem. B 2025, 13, 12624–12639. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Cheng, Y.X.; Gong, X.; Yang, J.; Zheng, G.Z.; Zheng, Y.; Li, Y.J.; Xu, Y.S.; Nie, G.; Xie, X.; Chen, M.W.; et al. A touch-actuated glucose sensor fully integrated with microneedle array and reverse iontophoresis for diabetes monitoring. Biosens. Bioelectron. 2022, 203, 114026. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Chinnadayyala, S.R.; Cho, S. Porous Platinum Black-Coated Minimally Invasive Microneedles for Non-Enzymatic Continuous Glucose Monitoring in Interstitial Fluid. Nanomaterials 2021, 11, 37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Dervisevic, M.; Alba, M.; Yan, L.; Senel, M.; Gengenbach, T.R.; Prieto-Simon, B.; Voelcker, N.H. Transdermal Electrochemical Monitoring of Glucose via High-Density Silicon Microneedle Array Patch. Adv. Funct. Mater. 2022, 32, 2009850. [Google Scholar] [CrossRef] [Scilit]
  14. Ribet, F.; Stemme, G.; Roxhed, N. Real-time intradermal continuous glucose monitoring using a minimally invasive microneedle-based system. Biomed. Microdevices 2018, 20, 101. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Sharifuzzaman, M.; Do Shin, Y.; Yoo, J.; Reza, M.S.; Kim, Y.R.; Park, J.Y. An oxygen-insensitive and minimally invasive polymeric microneedle sensor for continuous and wide-range transdermal glucose monitoring. Talanta 2023, 263, 124747. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Bakhshandeh, F.; Zheng, H.J.; Barra, N.G.; Sadeghzadeh, S.; Ausri, I.; Sen, P.; Keyvani, F.; Rahman, F.; Quadrilatero, J.; Liu, J.W.; et al. Wearable Aptalyzer Integrates Microneedle and Electrochemical Sensing for In Vivo Monitoring of Glucose and Lactate in Live Animals. Adv. Mater. 2024, 36, e2313743. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Chen, Y.; Fan, H.X.; Liu, W.H.; Wang, J.L.; Wang, T.Y.; Yang, R.; Zhang, L.B.; Shang, L.; Wen, D. Wearable Microneedle Patch Integrated with Metal Hydrogel-Based Signal Probe for Dermal Interstitial Fluid Protein Biomarkers Monitoring. Adv. Mater. 2026, 38, e14242. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. GhavamiNejad, A.; Flynn, C.D.; Geraili, A.; Mirzaie, S.; Esmaeili, F.; Zargartalebi, H.; Ahmed, S.; Juska, V.B.; Das, J.; Abdrabou, A.; et al. Continuous insulin monitoring using an antibody-protecting zwitterionic microneedle patch. Nat. Biomed. Eng. 2026, 10, 445–457. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Sadeghzadeh, S.; Li, P.; Zheng, H.J.; Ausri, I.R.; GhavamiNejad, P.; Caron-Godon, C.; Devries, M.C.; Graham, M.; Quadrilatero, J.; Poudineh, M. Functional wearable hydrogel microneedle platform for continuous ketone monitoring: Translating from rodents to humans. Biosens. Bioelectron. 2026, 304, 118640. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Zheng, H.J.; Keyvani, F.; Sadeghzadeh, S.; Mantaila, D.F.; Rahman, F.A.; Quadrilatero, J.; Poudineh, M. Rapid miRNA detection in skin interstitial fluid using a hydrogel microneedle patch integrated with DNA probes and graphene oxide. Lab Chip 2024, 24, 4989–4997. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Bollella, P.; Sharma, S.; Cass, A.E.G.; Antiochia, R. Minimally-invasive Microneedle-based Biosensor Array for Simultaneous Lactate and Glucose Monitoring in Artificial Interstitial Fluid. Electroanalysis 2019, 31, 374–382. [Google Scholar] [CrossRef] [Scilit]
  22. Majd, S.M. Hydrogel-coated microneedle biosensor for selective and low-potential glucose detection in skin-mimicking interstitial fluid phantoms. Talanta 2026, 297, 128555. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Reza, M.S.; Seonu, S.; Abu Zahed, M.; Asaduzzaman, M.; Song, H.; Jeong, S.H.; Park, J.Y. Reduced graphene oxide-functionalized polymer microneedle for continuous and wide-range monitoring of lactate in interstitial fluid. Talanta 2024, 270, 125582. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Reza, M.S.; Song, H.; Islam, Z.; Kim, D.; Go, J.; Park, J.Y. A perfluorinated sulfonic acid-based double-layered membrane-coated polymeric microneedle glucose sensor with wide linear range for long-term stable monitoring. Chem. Eng. J. 2026, 529, 172668. [Google Scholar] [CrossRef] [Scilit]
  25. Dervisevic, M.; Esser, L.; Chen, Y.P.; Alba, M.; Prieto-Simon, B.; Voelcker, N.H. High-density microneedle array-based wearable electrochemical biosensorfor detection of insulin in interstitial fluid. Biosens. Bioelectron. 2025, 271, 116995. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Fakeih, E.; Shetty, S.S.; Hanif, W.; Mutabagani, K.; Salama, K.N.; Alsulaiman, D. A Microneedle-Based IgE Aptasensor for Transdermal Detection of Food Allergy Sensitization. ACS Mater. Lett. 2025, 7, 3595–3603. [Google Scholar] [CrossRef] [Scilit]
  27. Friedel, M.; Werbovetz, B.; Drexelius, A.; Watkins, Z.; Bali, A.; Plaxco, K.W.; Heikenfeld, J. Continuous molecular monitoring of human dermal interstitial fluid with microneedle-enabled electrochemical aptamer sensors. Lab Chip 2023, 23, 3289–3299. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Keyvani, F.; Ghavaminejad, P.; Saleh, M.A.; Soltani, M.; Zhao, Y.S.; Sadeghzadeh, S.; Shakeri, A.; Chelle, P.; Zheng, H.J.; Rahman, F.A.; et al. Integrated Electrochemical Aptamer Biosensing and Colorimetric pH Monitoring via Hydrogel Microneedle Assays for Assessing Antibiotic Treatment. Adv. Sci. 2024, 11, e2309027. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Lin, S.; Cheng, X.; Zhu, J.; Wang, B.; Jelinek, D.; Zhao, Y.; Wu, T.Y.; Horrillo, A.; Tan, J.; Yeung, J.; et al. Wearable microneedle-based electrochemical aptamer biosensing for precision dosing of drugs with narrow therapeutic windows. Sci. Adv. 2022, 8, eabq4539. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Yuan, R.Q.; Cai, J.; Li, J.; Xu, Y.X.; Ma, J.F.; Wang, L.H.; Su, S. Integrated Microneedle Aptasensing Platform toward Point-of-Care Monitoring of Bacterial Infections and Treatment. ACS Sens. 2025, 10, 5684–5693. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Zhou, Y.; He, L.; Zhang, M.; Chen, M.J.; Wu, Y.C.; Liu, L.M.; Qi, L.L.; Zhang, B.; Yang, X.H.; He, X.X.; et al. An aptamer-responsive microneedle patch sensor platform combining with hybridization chain reaction amplification for detection of steroid hormone cortisol in skin interstitial fluid. Biosens. Bioelectron. 2025, 269, 116935. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Dervisevic, M.; Alba, M.; Adams, T.E.; Prieto-Simon, B.; Voelcker, N.H. Electrochemical immunosensor for breast cancer biomarker detection using high-density silicon microneedle array. Biosens. Bioelectron. 2021, 192, 113496. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Palma, A.; Di Natale, C.; Tammaro, D.; Lagreca, E.; Giordano, G.; Russo, S.; Vitiello, G.; Ferraro, V.; Vespini, V.; Grilli, S.; et al. Colorimetric sensing for transdermal phospho-Tau 181 detection mediated by wearable microneedle functionalized with gold nanoparticle (MN-AuNP). Talanta 2026, 300, 129198. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  34. Xu, J.X.; Yang, B.; Kong, J.L.; Zhang, Y.J.; Fang, X.E. Real-Time Monitoring and Early Warning of a Cytokine Storm In Vivo Using a Wearable Noninvasive Skin Microneedle Patch. Adv. Healthc. Mater. 2023, 12, 2203133. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  35. Yang, J.H.; Seong, K.Y.; Kang, M.; Jang, S.; Yang, S.Y.; Hahn, Y.K. Turbulence-enhanced microneedle immunoassay platform (TMIP) for high-precision biomarker detection from skin interstitial fluid. Biosens. Bioelectron. 2025, 282, 117480. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  36. Kadian, S.; Sahoo, S.S.; Kumari, P.; Narayan, R.J. Machine learning enabled onsite electrochemical detection of lidocaine using a microneedle array integrated screen printed electrode. Electrochim. Acta 2024, 475, 143664. [Google Scholar] [CrossRef] [Scilit]
  37. Kadian, S.; Sahoo, S.S.; Kumari, P.; Shukla, S.; Narayan, R.J. Minimally invasive detection of buprenorphine using a carbon-coated 3D-printed microneedle array. Microchim. Acta 2024, 191, 672. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  38. Kadian, S.; Sahoo, S.S.; Munshe, F.; Shukla, S.; Narayan, R.J. Laser-induced graphene on the surface of carbon-coated 3D-printed microneedle arrays for minimally invasive electrochemical detection of olanzapine. J. Mater. Chem. B 2026, 14, 2630–2643. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  39. Li, Y.; Wang, Y.Q.; Mei, R.C.; Lv, B.Q.; Zhao, X.Z.; Bi, L.Y.; Xu, H.; Chen, L.X. Hydrogel-Coated SERS Microneedles for Drug Monitoring in Dermal Interstitial Fluid. ACS Sens. 2024, 9, 2567–2574. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  40. Zhu, J.L.; Cheng, X.B.; Bahramian, M.; Yao, K.M.; Li, Z.Q.; Hu, B.T.; Wu, T.Y.; Sabet, K.A.; Cui, J.R.; Tan, J.W.; et al. Resilient nanostructured bioanalytic microneedle longitudinally monitors preclinical renal and hepatic drug clearance and dysfunction. Sci. Transl. Med. 2026, 18, eadr5493. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  41. Wang, K.; Ding, Q.H.; Qi, M.L.; Zhang, W.; Hou, Y.X.; Cao, R.D.; Li, C.Y.; Xu, L.; Wang, L.; Kim, J.S. Integrated Bilayer Microneedle Dressing and Triboelectric Nanogenerator for Intelligent Management of Infected Wounds. Adv. Funct. Mater. 2024, 34, 2316820. [Google Scholar] [CrossRef] [Scilit]
  42. Yang, J.B.; Zheng, S.T.; Ma, D.Y.; Zhang, T.; Huang, X.S.; Huang, S.; Chen, H.J.; Wang, J.; Jiang, L.L.; Xie, X. Masticatory system-inspired microneedle theranostic platform for intelligent and precise diabetic management. Sci. Adv. 2022, 8, abo6900. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  43. Fratus, M.; Alam, M.A. Theory of nanostructured sensors integrated in/on microneedles for diagnostics and therapy. Biosens. Bioelectron. 2024, 255, 116238. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  44. Zhou, S.C.; Chino, Y.; Kasama, T.; Miyake, R.; Mitsuzawa, S.; Luan, Y.A.; Ahmad, N.B.; Hibino, H.; Takai, M. Biocompatible Core-Shell Microneedle Sensor Filled with Zwitterionic Polymer Hydrogel for Rapid Continuous Transdermal Monitoring. ACS Nano 2024, 18, 26541–26559. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  45. Abbasiasl, T.; Mirlou, F.; Mirzajani, H.; Bathaei, M.J.; Istif, E.; Shomalizadeh, N.; Cebecioglu, R.E.; Özkahraman, E.E.; Yener, U.C.; Beker, L. A Wearable Touch-Activated Device Integrated with Hollow Microneedles for Continuous Sampling and Sensing of Dermal Interstitial Fluid. Adv. Mater. 2023, 36, 2304704. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  46. Yang, Y.; Wang, X.Y.; Hu, Y.X.; Liu, Z.Y.; Ma, X.; Feng, F.; Zheng, F.; Guo, X.L.; Liu, W.Y.; Liao, W.T.; et al. Rapid enrichment and SERS differentiation of various bacteria in skin interstitial fluid by 4-MPBA-AuNPs-functionalized hydrogel microneedles. J. Pharm. Anal. 2025, 15, 101152. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  47. Miranda, B.; Battisti, M.; De Martino, S.; Nocerino, V.; Dardano, P.; De Stefano, L.; Cangiano, G. Hollow Microneedle-based Plasmonic Sensor for on Patch Detection of Molecules in Dermal Interstitial Fluid. Adv. Mater. Technol. 2023, 8, 2300037. [Google Scholar] [CrossRef] [Scilit]
  48. Guo, Y.T.; Shang, Y.H.; Han, X.K.; Tang, Y.J.; Ma, T.; Shen, H.D.; Guo, Y.; Wang, X.; Wu, D.B.; Wang, Q.G. Carbon-Nanotube Synergized Robust Enzymatic-Fuel-Cell in Gel Microneedle for Self-Powered Monitoring and Forecasting. Adv. Mater. 2025, 37, e2313837. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  49. Han, J.H.; Kim, C.R.; Min, C.H.; Kim, M.J.; Kim, S.N.; Ji, H.B.; Bin Yoon, S.; Lee, C.L.; Bin Choy, Y. Microneedles coated with composites of phenylboronic acid-containing polymer and carbon nanotubes for glucose measurements in interstitial fluids. Biosens. Bioelectron. 2023, 238, 115571. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  50. Jin, D.L.; Xu, Z.J.; Zhao, H.Y.; Deng, S.L.; Qu, Z.Z.; Dou, R.Y.; Liu, W.L. A minimally invasive sensing system based on hydrogel microneedle patches and Au/Cu2O nanospheres modified screen-printed carbon electrode for glucose monitoring in interstitial skin fluid. Microchem. J. 2024, 205, 111367. [Google Scholar] [CrossRef] [Scilit]
  51. Zheng, M.J.; Zhang, Y.Y.; Hu, T.L.; Xu, C.J. A skin patch integrating swellable microneedles and electrochemical test strips for glucose and alcohol measurement in skin interstitial fluid. Bioeng. Transl. Med. 2023, 8, e10413. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  52. Ai, D.K.; Tang, X.; Meng, Z.L.; Yu, Y.; Guo, X.X.; Wang, Y.P. Porous microneedle-based electrochemical sensor for potassium and glucose in skin interstitial fluid. Anal. Methods 2025, 17, 7541–7550. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  53. Hao, X.K.; Qin, C.L.; He, C.W.; Yuan, Q.C.; Yang, P.J.; Wen, Y.H.; Wu, Y.J.; Cui, R.W.; Zhang, Y.Q.; Chen, W.; et al. In situ detection of bacteria from skin interstitial fluid via CRISPR microneedles: An amplification-free platform for point-of-care diagnostics. Biosens. Bioelectron. 2026, 293, 118123. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  54. Ju, J.; Hsieh, C.M.; Tian, Y.; Kang, J.; Chia, R.N.; Chang, H.; Bai, Y.R.; Xu, C.J.; Wang, X.M.; Liu, Q. Surface Enhanced Raman Spectroscopy Based Biosensor with a Microneedle Array for Minimally Invasive In Vivo Glucose Measurements. ACS Sens. 2020, 5, 1777–1785. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  55. Li, Z.H.; Sun, W.; Shi, Z.; Cao, Y.Z.; Wang, Y.W.; Lu, D.X.; Jiang, M.Y.; Wang, Z.F.; Marty, J.L.; Zhu, Z.G. Development of an osmosis-assisted hollow microneedle array integrated with dual-functional electrochemical sensor for urea and pH monitoring in interstitial fluid. Sens. Actuators B Chem. 2025, 422, 136606. [Google Scholar] [CrossRef] [Scilit]
  56. Lian, Z.W.; Ou, T.L.; Men, K.; Wei, Q.H.; Wei, F.; Zhao, H.B.; Yang, Z.M.; Tu, H.L. High-density AuNP-decorated microneedle electrochemical aptasensor for minimally invasive CEA detection in interstitial fluid. Microchim. Acta 2025, 192, 1–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  57. Tortolini, C.; Cass, A.E.G.; Pofi, R.; Lenzi, A.; Antiochia, R. Microneedle-based nanoporous gold electrochemical sensor for real-time catecholamine detection. Microchim. Acta 2022, 189, 180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  58. Chen, C.C.; Fu, Y.H.; Lin, Y.H.; Liu, Y.; Du, D.; Qiu, K.Y. 3D-printed hollow microneedle-based electrochemical sensor for wireless glucose monitoring. Analyst 2026, 151, 1182–1194. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  59. Rahman, F.; Ryan, A.; Bocchino, A.; Galvin, P.; Teixeira, S.R. Microneedle-based electrochemical sensors for real-time pH and sodium monitoring in physiological environments. Sens. Bio Sens. Res. 2025, 48, 100777. [Google Scholar] [CrossRef] [Scilit]
  60. Yu, Y.; Liu, S.S.; Meng, Z.L.; Dong, X.X.; Lao, J.C.; Wang, Y.P. Macroporous-channel hollow microneedles enable vacuum-free interstitial fluid sampling and on-patch sensing. ACTA Biomater. 2026, 214, 572–583. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  61. Zhu, J.C.; Wang, W.L.; Chen, G.; Gao, T.; Gao, Z.Y.; Peng, L.; Wang, L.W.; Cai, W. A high-performance wearable microneedle sensor based on a carboxylated carbon nanotube-carbon nanotube composite electrode for the simultaneous detection of uric acid and dopamine. Microchem. J. 2024, 206, 111607. [Google Scholar] [CrossRef] [Scilit]
  62. Liu, J.X.; Liu, J.; Liang, Y.Y.; Yang, J.; Lin, Y.P.; Li, Y.C. Microneedle-Based Electrochemical Array Patch for Ultra-Antifouling and Ultra-Anti-Interference Monitoring of Subcutaneous Oxygen. Anal. Chem. 2024, 97, 373–381. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  63. Zhu, J.C.; Wang, L.W.; Xu, S.X.; Peng, L.; Gao, Z.Y.; Liu, S.T.; Xi, S.B.; Ma, S.P.; Cai, W. A high-performance wearable microneedle sensor based on a prussian blue-carbon nanotube composite electrode for the detection of hydrogen peroxide and glucose. Sens. Actuators B Chem. 2024, 419, 136436. [Google Scholar] [CrossRef] [Scilit]
  64. Jing, L.Y.; Fan, Y.K.; Chen, B.Z.; Li, D.H.; He, Y.T.; Zhang, G.L.; Liang, L.; Du, J.; Wang, Y.; Guo, X.D. An aptamer-integrated conductive microneedle biosensor for real-time transdermal cortisol monitoring. Chem. Eng. J. 2024, 502, 157488. [Google Scholar] [CrossRef] [Scilit]
  65. Yang, B.; Kong, J.L.; Fang, X.E. Programmable CRISPR-Cas9 microneedle patch for long-term capture and real-time monitoring of universal cell-free DNA. Nat. Commun. 2022, 13, 3999. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  66. Yi, K.X.; Wang, Y.T.; Shi, K.Q.; Chi, J.J.; Lyu, J.X.; Zhao, Y.J. Aptamer-decorated porous microneedles arrays for extraction and detection of skin interstitial fluid biomarkers. Biosens. Bioelectron. 2021, 190, 113404. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  67. Parrilla, M.; Detamornrat, U.; Domínguez-Robles, J.; Tunca, S.; Donnelly, R.F.; De Wael, K. Wearable Microneedle-Based Array Patches for Continuous Electrochemical Monitoring and Drug Delivery: Toward a Closed-Loop System for Methotrexate Treatment. ACS Sens. 2023, 8, 4161–4170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  68. Dragan, A.M.; Parrilla, M.; Cambré, S.; Domínguez-Robles, J.; Detamornrat, U.; Donnelly, R.F.; Oprean, R.; Cristea, C.; De Wael, K. Microneedle array-based electrochemical sensor functionalized with SWCNTs for the highly sensitive monitoring of MDMA in interstitial fluid. Microchem. J. 2023, 193, 109257. [Google Scholar] [CrossRef] [Scilit]
  69. Kolluru, C.; Gupta, R.; Jiang, Q.S.; Williams, M.; Derami, H.G.; Cao, S.S.; Noel, R.K.; Singamaneni, S.; Prausnitz, M.R. Plasmonic Paper Microneedle Patch for On-Patch Detection of Molecules in Dermal Interstitial Fluid. ACS Sens. 2019, 4, 1569–1576. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  70. Wu, Y.; Tehrani, F.; Teymourian, H.; Mack, J.; Shaver, A.; Reynoso, M.; Kavner, J.; Huang, N.; Furmidge, A.; Duvvuri, A.; et al. Microneedle Aptamer-Based Sensors for Continuous, Real-Time Therapeutic Drug Monitoring. Anal. Chem. 2022, 94, 8335–8345. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  71. Ding, L.; Zhang, H.Z.; Li, Y.; Kameoka, J. Lyocell-modal thread microfluidic platform integrated with a microneedle sensor for lactate detection in saliva. Lab Chip 2026, 26, 2804–2819. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  72. Mugo, S.M.; Dhanjai; Lu, W.H.; Robertson, S. A Multipurpose and Multilayered Microneedle Sensor for Redox Potential Monitoring in Diverse Food Analysis. Biosensors 2022, 12, 1001. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  73. Mugo, S.M.; Lu, W.H.; Wood, M.; Lemieux, S. Wearable microneedle dual electrochemical sensor for simultaneous pH and cortisol detection in sweat. Electrochem. Sci. Adv. 2022, 2, e2100039. [Google Scholar] [CrossRef] [Scilit]
  74. Mugo, S.M.; Robertson, S.V.; Lu, W.H. A molecularly imprinted electrochemical microneedle sensor for multiplexed metabolites detection in human sweat. Talanta 2023, 259, 124531. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  75. Parrilla, M.; Sena-Torralba, A.; Steijlen, A.; Morais, S.; Maquieira, A.; De Wael, K. A 3D-printed hollow microneedle-based electrochemical sensing device for in situ plant health monitoring. Biosens. Bioelectron. 2024, 251, 116131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  76. Tan, T.; He, J.C.; Chen, X.Y.; Feng, Q.C.; Pang, X.X.; Nong, Y.X. Self-referencing nano-microneedle based on WO3 for single-cell analysis of pH. Microchem. J. 2026, 222, 117320. [Google Scholar] [CrossRef] [Scilit]
  77. Khazaei, M.; Hosseinikebria, S.S.; Dervisevic, M.; Li, J.; Razal, J.M.; Voelcker, N.H.; Nilghaz, A. Enhancing Food Safety with Microneedle-Based Biosensors: Real-Time Monitoring of Fish Freshness. ACS Sens. 2025, 10, 9315–9322. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  78. Zou, K.; Hao, Z.; Liu, Y.; Zhang, R.Z.; Li, X.Y.; Zhang, L.B. In situ enrichment and ultrasensitive analysis of interstitial fluid miRNA enabled by hydrogel microneedles coupled with DNA-gated metal-organic frameworks. Chem. Commun. 2025, 61, 7470–7473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  79. Zhang, R.; Rana, M.S.; Huang, L.; Qian, K. An antibacterial sensitive wearable biosensor enabled by engineered metal-boride-based organic electrochemical transistors and hydrogel microneedles. J. Mater. Chem. A 2025, 13, 18590–18599. [Google Scholar] [CrossRef] [Scilit]
  80. Li, X.D.; Lv, J.T.; Zhao, J.H.; Ling, G.X.; Zhang, P. Swellable colorimetric microneedles for glucose detection based on glucose oxidase-like gold nanoparticles. Anal. Chim. Acta 2024, 1288, 342152. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  81. Iftikhar, T.; Imran, T.; He, J.H.; Zhang, C.J.; Xie, Y.T.; Ye, H.T.; Su, L. MOFs-on-MOFs modified wearable electrochemical microneedle array for uric acid detection. Biosens. Bioelectron. 2026, 294, 118246. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  82. Chen, J.Y.; Zheng, S.T.; Cai, Y.J.; Yao, C.J.; Li, X.T.; Zhou, C.H.; Yan, L.W.; Qiu, F.R.; Wang, X.Z.; Jiang, L.L.; et al. Vertical graphene-coated core-shell microneedle as miniatured sensor for in vivo glucose monitoring. Microsyst. Nanoeng. 2026, 12, 62. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  83. Dervisevic, M.; Fornerod, M.J.J.; Harberts, J.; Zangabad, P.S.; Voelcker, N.H. Wearable Microneedle Patch for Transdermal Electrochemical Monitoring of Urea in Interstitial Fluid. ACS Sens. 2024, 9, 932–941. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  84. Li, G.; Yu, Y.; Meng, Z.L.; Ai, D.K.; Li, M.M.; Wang, Y.P. Bio-inspired microneedles with hierarchical microchannels for rapid interstitial fluid collection and analysis. Lab Chip 2025, 25, 3016–3026. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  85. Chung, J.H.; Chowdhury, J.R.; Fan, K.P.; Liu, K.L.; Nahak, B.K.; Ganguly, A.; Sharma, M.K.; Parashar, P.; Lee, S.; Lin, Z.H. Thermoelectric-driven self-powered microneedle sensor for continuous interstitial fluid glucose monitoring. Nano Energy 2025, 146, 111505. [Google Scholar] [CrossRef] [Scilit]
  86. Skaria, E.; Patel, B.A.; Flint, M.S.; Ng, K.W. Poly(lactic acid)/Carbon Nanotube Composite Microneedle Arrays for Dermal Biosensing. Anal. Chem. 2019, 91, 4436–4443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  87. Dervisevic, M.; Harberts, J.; Sánchez-Salcedo, R.; Voelcker, N.H. 3D Polymeric Lattice Microstructure-Based Microneedle Array for Transdermal Electrochemical Biosensing. Adv. Mater. 2024, 36, e2412999. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  88. Kandan, M.P.; David Stephen, J.B.; Suseela, S.B.P. Development of Electrochemical Sensors for Blood Glucose Detection with Wide Range Using MWCNT-Chitosan-A Microneedle Approach. IEEE Sens. Lett. 2026, 10, 1–4. [Google Scholar] [CrossRef] [Scilit]
  89. Senel, M.; Dervisevic, M.; Voelcker, N.H. Gold microneedles fabricated by casting of gold ink used for urea sensing. Mater. Lett. 2019, 243, 50–53. [Google Scholar] [CrossRef] [Scilit]
  90. Huang, X.S.; Huang, S.; Zheng, S.T.; Liang, B.M.; Zhang, T.; Yue, W.; Liu, F.M.; Shi, P.; Xie, X.; Chen, H.J. Fabrication of Multiple-Channel Electrochemical Microneedle Electrode Array via Separated Functionalization and Assembly Method. Biosensors 2024, 14, 243. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  91. Kim, J.; Kim, H.; Park, S.; Hong, H.; Kim, Y.J.; Lee, J.; Kim, J.; Cho, S.W.; Ryu, W. Individually-addressable composite microneedle electrode array by mold-and-place method for glucose detection. Sens. Actuators B Chem. 2024, 401, 134884. [Google Scholar] [CrossRef] [Scilit]
  92. Sun, H.Y.; Wang, S.D.; Wang, H.X.; Zeng, Q.K.; Wang, F.B.; Zheng, Y.B.; Haick, H.; Shi, G.Y.; Zhang, M. Stick-and-sensing microneedle patch for personalized nutrition management. Sens. Actuators B Chem. 2024, 418, 136207. [Google Scholar] [CrossRef] [Scilit]
  93. Jin, Q.C.; Chen, H.J.; Li, X.L.; Huang, X.S.; Wu, Q.N.; He, G.; Hang, T.; Yang, C.D.; Jiang, Z.; Li, E.L.; et al. Reduced Graphene Oxide Nanohybrid-Assembled Microneedles as Mini-Invasive Electrodes for Real-Time Transdermal Biosensing. Small 2019, 15, e1804298. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  94. Ming, T.; Lan, T.T.; Yu, M.X.; Duan, X.; Cheng, S.H.; Wang, H.; Deng, J.; Kong, D.L.; Yang, S.; Shen, Z.Y. A novel electrochemical microneedle sensor for highly sensitive real time monitoring of glucose. Microchem. J. 2024, 207, 112021. [Google Scholar] [CrossRef] [Scilit]
  95. Parrilla, M.; Claes, N.; Toyos-Rodríguez, C.; Dricot, C.; Steijlen, A.; Lebeer, S.; Bals, S.; De Wael, K. Wearable 3D-printed solid microneedle voltammetric sensors based on nanostructured gold for uric acid monitoring. Biosens. Bioelectron. 2025, 289, 117934. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  96. Reynoso, M.; Chang, A.Y.; Wu, Y.; Murray, R.; Suresh, S.; Dugas, Y.; Wang, J.S.; Arroyo-Currás, N. 3D-printed, aptamer-based microneedle sensor arrays using magnetic placement on live rats for pharmacokinetic measurements in interstitial fluid. Biosens. Bioelectron. 2024, 244, 115802. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  97. Keyvani, F.; Zheng, H.J.; Kaysir, M.R.; Mantaila, D.F.; Nejad, P.G.; Rahman, F.A.; Quadrilatero, J.; Ban, D.Y.; Poudineh, M. A Hydrogel Microneedle Assay Combined with Nucleic Acid Probes for On-Site Detection of Small Molecules and Proteins. Angew. Chem. Int. Ed. 2023, 62, e202301624. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  98. Qi, M.; Fu, W.X.; Ying, X.D.; Zhu, B.Y.; Zhao, Z.Y.; Zhou, L.; Li, W.; Su, B. Microneedle Combined with an Electrochemical Lateral Flow Immunoassay Strip for Highly Sensitive and Wide-Range Detection of Protein Biomarkers by Increasing the Reaction Contact Area. Anal. Chem. 2025, 97, 10638–10645. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  99. Simas, M.V.; Olaniyan, P.O.; Hati, S.; Davis, G.A., Jr.; Anspach, G.; Goodpaster, J.V.; Manicke, N.E.; Sardar, R. Superhydrophobic Surface Modification of Polymer Microneedles Enables Fabrication of Multimodal Surface-Enhanced Raman Spectroscopy and Mass Spectrometry Substrates for Synthetic Drug Detection in Blood Plasma. ACS Appl. Mater. Interfaces 2023, 15, 46681–46696. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  100. Zhan, C.Y.; Liu, F.M.; Shen, Z.R.; Huang, X.S.; Huang, S.; Li, X.L.; Liu, J.; Yang, J.; Xu, J.F.; Xie, X.; et al. A 3D-printed microneedle extraction system integrated with patterned electrodes for minimally invasive transdermal detection. Biomater. Sci. 2023, 11, 3737–3749. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  101. Teymourian, H.; Moonla, C.; Tehrani, F.; Vargas, E.; Aghavali, R.; Barfidokht, A.; Tangkuaram, T.; Mercier, P.P.; Dassau, E.; Wang, J. Microneedle-Based Detection of Ketone Bodies along with Glucose and Lactate: Toward Real-Time Continuous Interstitial Fluid Monitoring of Diabetic Ketosis and Ketoacidosis. Anal. Chem. 2020, 92, 2291–2300. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  102. Ashraf, G.; Wang, H.N.; Ahmed, K.; Xiong, H.W.; Kong, J.L.; Fang, X.E. Microneedle-Integrated FePc-MOF-MXene Nanozyme Patch for In Vivo L-Cysteine Monitoring. Adv. Mater. 2025, 37, e2502804. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  103. Oliveira, D.; Correia, B.P.; Sharma, S.; Moreira, F.T.C. Molecular Imprinted Polymers on Microneedle Arrays for Point of Care Transdermal Sampling and Sensing of Inflammatory Biomarkers. ACS Omega 2022, 7, 39039. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  104. Panicker, L.R.; Joy, A.; Anusree, P.R.; Kadian, S.; Narayan, R.; Padmesh, A.; Kotagiri, Y.G. Molecular imprinted polymer based microneedle-strip electrochemical sensor for label-free dopamine monitoring: Advancing neurological disorder Diagnostics. Chem. Eng. J. 2025, 516, 163870. [Google Scholar] [CrossRef] [Scilit]
  105. Zhu, J.C.; Wang, W.L.; Wang, L.W.; Cui, S.Y.; Han, D.X.; Liu, S.T.; Ma, S.P.; Xi, S.B.; Cai, W.; Peng, L. A high-performance wearable microneedle sensor based on CNT/CCNT@Cu-ZIF-67 composites for simultaneous detection of uric acid and dopamine. Chem. Eng. J. 2025, 515, 163869. [Google Scholar] [CrossRef] [Scilit]
  106. Lv, M.R.; Wang, L.; Hou, Y.T.; Qiao, X.J.; Luo, X.L. A wearable antifouling electrochemical sensor integrated with an antimicrobial microneedle array for uric acid detection in interstitial fluid. Anal. Chim. Acta 2025, 1339, 343610. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  107. Ming, T.; Lan, T.T.; Yu, M.X.; Wang, H.; Deng, J.; Kong, D.L.; Yang, S.; Shen, Z.Y. Platinum Black/Gold Nanoparticles/Polyaniline Modified Electrochemical Microneedle Sensors for Continuous In Vivo Monitoring of pH Value. Polymers 2023, 15, 2796. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  108. Mokhtar, S.M.A.; Yamada, M.; Prow, T.W.; Moore, M.; Strudwick, X.L.; Evans, D.R. PEDOT coated microneedles towards electrochemically assisted skin sampling. J. Mater. Chem. B 2023, 11, 5021–5031. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  109. Bashir, M.; Hussain, S.; Cialla-May, D.; Popp, J.; Alabudahash, M.; Zourob, M. A Wearable Microneedle-Integrated Multiplexed Photonic Aptasensor for the Detection of Illicit Drugs in Interstitial Fluid. Anal. Chem. 2026, 98, 4263–4274. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  110. Gu, Z.M.; Zhao, D.; He, H.Y.; Wang, Z.H. SERS-Based Microneedle Biosensor for In Situ and Sensitive Detection of Tyrosinase. Biosensors 2024, 14, 202. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  111. Liu, Y.; Li, W.T.; Lu, Z.Y.; Cai, H.Y.; Yuan, R.L.; Yang, Y.Q.; Qiao, X.Z. A microneedle-based SERS sensor for simultaneous detection of pH and uric acid in interstitial fluid. Microchem. J. 2026, 222, 117164. [Google Scholar] [CrossRef] [Scilit]
  112. Zhu, G.; Wang, Y.; Yang, X.; Chen, C.; Lv, X.Y.; Huang, Y.; Zhao, X.W. A porous SERS microneedle for multiplex detection of glucose, uric acid, and cholesterol in interstitial fluid. Anal. Chim. Acta 2025, 1380, 344788. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  113. Zhu, G.; Liu, C.; Lu, Y.; Mo, X.F.; Dong, J.; Xu, K.; Huang, Y.; Chen, C.; Lv, X.Y.; Yang, X.; et al. Porous SERS Microneedles Integrating Sampling and Sensing for Interstitial Glucose Detection. ACS Appl. Nano Mater. 2025, 8, 7867–7875. [Google Scholar] [CrossRef] [Scilit]
  114. Keerthanaa, M.R.; Panicker, L.R.; Narayan, R.; Kotagiri, Y.G. Biopolymer-protected graphene-Fe3O4 nanocomposite based wearable microneedle sensor: Toward real-time continuous monitoring of dopamine. RSC Adv. 2024, 14, 7131–7141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  115. Reis, A.C.D.; de Castro-Kochi, A.C.H.; Rojas, J.E.U.; Chiaro, D.A.; Guha, S.; King, G.M.; de Oliveira, V.L.; de Araujo, D.R.; Tofoli, G.R.; Romero, M.; et al. Polypyrrole-Coated Microneedle Platform for Offline Electrochemical Detection of Interferon-Alpha in Interstitial Fluid. ACS Appl. Bio Mater. 2026, 9, 2419–2433. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  116. Downs, A.M.; Bolotsky, A.; Weaver, B.M.; Bennett, H.; Wolff, N.; Polsky, R.; Miller, P.R. Microneedle electrochemical aptamer-based sensing: Real-time small molecule measurements using sensor-embedded, commercially-available stainless steel microneedles. Biosens. Bioelectron. 2023, 236, 115408. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  117. Bollella, P.; Sharma, S.; Cass, A.E.G.; Tasca, F.; Antiochia, R. Minimally Invasive Glucose Monitoring Using a Highly Porous Gold Microneedles-Based Biosensor: Characterization and Application in Artificial Interstitial Fluid. Catalysts 2019, 9, 580. [Google Scholar] [CrossRef] [Scilit]
  118. Hwa, K.Y.; Subramani, B.; Chang, P.W.; Chien, M.N.; Huang, J.T. Transdermal Microneedle Array-based Sensor for Real Time Continuous Glucose Monitoring. Int. J. Electrochem. Sci. 2015, 10, 2455–2466. [Google Scholar] [CrossRef] [Scilit]
  119. Tawakey, S.H.; Mansour, M.; Soltan, A.; Salim, A.I. Early detection of hypo/hyperglycemia using a microneedle electrode array-based biosensor for glucose ultrasensitive monitoring in interstitial fluid. Lab Chip 2024, 24, 3958–3972. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  120. Sun, X.Y.; Chen, K.Q.; Wang, Y.; Zhang, Z.W.; Lin, J.F.; Liu, G.L.; Meng, D.H.; Dong, J.; Huang, Y. A SERS-active microneedle array for rapid and minimally invasive lactic acid detection. Anal. Chim. Acta 2025, 1373, 344469. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  121. Yin, S.J.; Yu, Z.Q.; Song, N.N.; Guo, Z.J.; Li, W.; Ma, J.H.; Wang, X.Y.; Liu, J.Y.; Liang, M.M. A long lifetime and highly sensitive wearable microneedle sensor for the continuous real-time monitoring of glucose in interstitial fluid. Biosens. Bioelectron. 2024, 244, 115822. [Google Scholar] [CrossRef] [Scilit] [PubMed]
Figure 1. Scope positioning of HFMN-enabled ISF biosensing and therapeutic monitoring. The figure maps evidence classes along two conceptual axes: increasing platform relevance to HFMNs and increasing therapeutic proximity. Core HFMN and hydrogel-integrated ISF biosensors occupy the highest platform-relevance region, while therapeutic drug-monitoring and sensing-plus-delivery systems move toward greater therapeutic proximity. Comparator ISF microneedle biosensors and peripheral or non-ISF comparators are positioned as contextual evidence rather than central support for HFMN-enabled therapeutic monitoring. The highlighted upper-right region represents the highest-priority evidence space, where hydrogel-forming or hydrogel-integrated platforms intersect with therapeutic monitoring, delivery, or theranostic function (Prepared with the assistance of Gemini NotebookLM pro and OpenAI ChatGPT Plus).
Jnt 07 00019 g001
Figure 2. Architecture-controlled ISF access in hydrogel-forming microneedles. A hydrogel-forming microneedle first functions as a dry, mechanically competent structure for skin insertion, then hydrates and swells within the viable epidermis and dermis to access ISF. Hydration enables ISF uptake and analyte diffusion through the hydrogel network toward an integrated or coupled sensing interface. The inset distinguishes comparator routes in which hollow microneedles rely on lumen extraction, porous microneedles on capillary wicking, and solid microneedles on direct insertion of a sensing interface (Prepared with the assistance of Gemini NotebookLM pro and OpenAI ChatGPT Plus).
Jnt 07 00019 g002
Figure 3. Hydrated recognition–transduction interface in HFMN sensing. The schematic illustrates ISF analyte diffusion into a swollen HFMN or hydrogel microneedle sensing zone, immobilized recognition elements, signal-conversion surfaces, and stabilized readout. The main interface-level constraints are fouling, drift, cross-reactivity, receptor instability, and coating loss, while stabilization strategies include hydrogel confinement, antifouling coatings, diffusion membranes, nanostructured conductors, and spatial separation (Prepared with the assistance of Gemini NotebookLM pro and OpenAI ChatGPT Plus).
Jnt 07 00019 g003
Figure 4. Integrated analytical-performance framework for HFMN-enabled monitoring. The figure shows the progression from hydrated ISF sampling to analytical signal generation, benchmark validation, failure-mode screening, and therapeutic-monitoring readiness. It emphasizes that low limit of detection alone is insufficient; reliable monitoring requires coordinated performance across ISF uptake, analyte diffusion, physiologically relevant sensing, comparator agreement, and resistance to biofouling, drift, insertion damage, and ISF–blood mismatch (Prepared with the assistance of Gemini NotebookLM pro and OpenAI ChatGPT Plus).
Jnt 07 00019 g004
Figure 5. Evidence gates for translating hydrogel-forming microneedles from ISF biosensing to therapeutic monitoring. The figure depicts the increasing evidentiary burden required to move HFMN and hydrogel-assisted microneedle systems from analytical feasibility to biological validation, comparator alignment, wearable readiness, and therapeutic-monitoring or closed-loop readiness. The right-hand outcomes distinguish monitoring-only systems, feedback-informed therapeutic monitoring, and true closed-loop or sensor-controlled drug delivery. The figure emphasizes that most current platforms remain concentrated in the earlier validation gates, whereas few reach delivery-capable or theranostic integration, and no confirmed autonomous closed-loop control is established in the cited evidence (Prepared with the assistance of Gemini NotebookLM pro and OpenAI ChatGPT Plus).
Jnt 07 00019 g005
Table 1. Scope-based evidence positioning for HFMN-enabled ISF biosensing and therapeutic monitoring.
Scope, Classification, and Therapeutic RelevanceWhat the Evidence DemonstratesBoundary or Unresolved PointReferences
Biosensing based on HFMNs, hydrogel-integrated microneedles, and hydrogel-mediated ISF accessHFMNs and hydrogel-integrated or hydrogel-mediated microneedles can access ISF or tissue-associated fluid and monitor clinically relevant metabolites, proteins, ions, nucleic acids, microbial targets, drugs, and wound biomarkers.Strong support exists for biosensing and monitoring, but evidence remains limited for direct therapeutic actuation or autonomous closed-loop control.[5,6,8,16,18,19,20,28,46,78]
Hydrogel-relevant systems not strictly based on HFMNsHydrogel coatings, swellable matrices, gel shells, PEGDA interfaces, and hydrogel-like sensing layers can support ISF uptake, analyte access, or wearable signal acquisition.Hydrogel functionality is often used for sampling or sensing support, not drug storage, controlled release, or feedback-triggered therapy.[4,7,17,22,31,39,47,48,50,51]
Comparator ISF microneedle biosensorsMicroneedle systems not based on hydrogels or HFMNs establish clinically relevant analytes, sampling strategies, and device architectures for ISF monitoring.These studies contextualize HFMNs but should not be treated as direct evidence for hydrogel-mediated sampling, diffusion, or delivery advantages.[40,45,52,53,55,56,57,59,60,64,65,66,67]
Therapeutic drug monitoring and pharmacokinetic assessmentMicroneedle platforms can track therapeutic drugs, toxic agents, illicit drugs, or treatment-associated biomarkers relevant to dosing, exposure, toxicity prevention, or response assessment.Most systems remain monitoring-only platforms; clinical dosing benefit and real-time treatment adjustment are not consistently demonstrated.[6,28,29,30,36,37,38,39,40,68]
Sensing-plus-delivery or theranostic platformsA small subset couples monitoring with drug delivery, electrical stimulation, insulin delivery, or wound-treatment functions.These are the closest examples to the manuscript’s therapeutic endpoint, but broad evidence for autonomous closed-loop therapy based on HFMNs remains limited.[8,41,42,67]
Framework and peripheral comparator evidenceReviews, theoretical models, and microneedle sensors outside ISF-centered or clinical contexts help frame translation, closed-loop concepts, and point-of-need sensing beyond HFMNs.These sources are useful for context only and should not expand the central claim beyond ISF biosensing and therapeutic monitoring enabled by HFMNs.[1,2,3,43,71,72,73,74,77,79]
Table 2. Hydrogel-forming microneedle architecture and ISF transport strategies relevant to biosensing and therapeutic monitoring.
Microneedle Architecture, Skin Interface, ISF Access, and Transport BehaviorHFMN-Centered InterpretationTechnical EvidenceReferences
Swellable HFMNs and hydrogel-mediated matrices for ISF extractionCore HFMN or hydrogel-mediated format in which the hydrogel penetrates skin, hydrates, and extracts or transfers ISF.PEGDA 10 × 10 array with 782 ± 10 µm needle length; MeHA/PVA patch with >0.1 N per needle strength and 400% swelling; swellable microneedles extracting approximately 6.87 µL per needle in 5 min with 0.21 N per needle penetration strength; two-layer patch absorbing 60.2 mg ISF in 10 min; hyaluronic acid methacryloyl (HA-MA), MeHA, and GelMA systems further supporting ISF biomarker extraction.[4,6,7,20,30,31,78,80]
Conductive HFMNs and hydrogel–electrode systemsIntegrated HFMN or hydrogel-microneedle formats in which the hydrated matrix contributes directly to sensing or electrode function.Dopamine-conjugated hyaluronic acid/PEDOT:PSS hydrogel microneedles with assessed swelling and mechanical strength; crosslinked MeHA/PEDOT:PSS/graphene oxide hydrogel microneedle electrode; PVA/chitosan/MXene HFMN dressing with PEDOT:PSS/graphene oxide electrodes and 384 S/m conductivity.[5,8,9]
Hydrogel-filled or hydrogel-coated hybridsRigid, hollow, or coated structures provide insertion strength, while hydrogel components mediate uptake, diffusion, or local transport.PEGDA hydrogel transducer inside hollow microneedle cavities; hydrogel-coated gold–silver core–shell (Au@Ag) substrate enabling mouse ISF drug monitoring within 10 min; alginate–PVA hydrogel encapsulation improving analyte diffusion; PLA hollow shells filled with zwitterionic hydrogel to reduce subcutaneous friction.[22,39,44,47]
Decoupled HFMNs and swellable sampling formatsHFMNs or swellable microneedles collect or transfer ISF, while sensing occurs on a coupled electrode, backing layer, or assay module.Graphene oxide–nucleic acid fluorescence module coupled to hydrogel microneedle extraction; flexible HMN-based platform combining ISF-extracting hydrogel microneedles with flexible electrodes; swellable microneedles using chitosan to route ISF to an electrochemical strip backing.[28,51,97]
Hollow, porous, capillary, and osmotic comparatorsPlatforms not based on HFMNs, or hybrid platforms, benchmark ISF access mechanisms against swelling-based hydrogel uptake.Hollow vacuum extraction to approximately −53 kPa with approximately 2 µL per needle per hour ISF collection; hollow array yielding 5.6 µL in 5 min; porous microneedles paired with PEG-loaded filter-paper decoupled extraction; MgCl2 osmosis-assisted HMNs; ETPTA porous microneedles with 6.694 m2/g surface area; macroporous-channel HMNs with rigid shell, interconnected pores, axial lumen, and paper-wick collectors; reverse iontophoresis after microneedle microchannel formation increasing glucose extraction flux by approximately 1.6-fold.[11,17,45,52,55,60,66]
Interface protection and diffusion controlStructural measures preserve microneedle function during insertion, hydration, and prolonged ISF exposure.Recessed microcavities protecting sensing layers; water-soluble protective layer dissolving after ISF contact; 1.25 wt% Nafion diffusion membrane; double-layer fluorinated copolymer diffusion barrier; only 8.4% signal decrease after four porcine-skin insertions; nanocavity bioelectrode supporting 6 days in vivo without structural degradation.[23,24,40,83,93,95]
Therapeutic monitoring and delivery-relevant architecturesISF drug tracking is broader than active delivery; delivery claims require demonstrated release, stimulation, or subcutaneous delivery.Flexible HMN-based and microneedle-based electrochemical aptamer biosensing (μNEAB) patches for antibiotic monitoring; hydrogel-coated microneedles for ISF drug monitoring; MeHA/PVA HFMN patch for fentanyl extraction; nanocavity bioelectrode for pharmacokinetic and drug-clearance monitoring; iontophoretic HMN array with anode and cathode for methotrexate delivery; dissolvable polyvinylpyrrolidone (PVP) antibiotic-loaded microneedles above stainless-steel microneedles; on-demand microneedle penetration enabling ISF exudation and subcutaneous insulin delivery.[6,28,29,39,40,41,42,67]
Peripheral non-ISF and nonclinical comparatorsUseful only for device-design principles; not evidence for dermal ISF behavior mediated by HFMNs.Plant hollow microneedle array with 25.9 ± 3.7 µm tip diameter, 228.2 ± 18.6 µm side-hole diameter, 20–40 N thumb-force tolerance, and 13.5 ± 1.1 µL plant-fluid extraction; sweat, saliva, fish-tissue, intracellular, nitrocellulose-membrane, food-matrix, and blood-plasma SERS or mass spectrometry platforms demonstrating comparator mechanics or non-clinical sensing.[71,72,73,74,75,76,77,79,98,99]
Table 3. Mechanism-level priorities for HFMN molecular recognition and signal transduction.
Molecular Recognition and Signal-Transduction StrategyHFMN- and HMN-Specific FunctionCritical Interpretation References
Hydrogel or porous microneedles as recognition-supporting matricesHydrated matrices host aptamers, antibodies, probe DNA, DNA-gated metal–organic frameworks (MOFs), zwitterionic stabilizers, or conductive hydrogel networks while enabling ISF contact.The evidence is strongest when the hydrogel actively stabilizes recognition chemistry rather than merely collecting ISF. Evidence remains promising but uneven for long-term receptor retention during swelling and wear.[18,20,31,44,66,78,97]
Enzymatic and mediated electrochemical metabolite sensingEnzymes are coupled to conductive supports, redox mediators, antifouling films, and diffusion-control membranes to convert catalytic turnover into current.This is the most mature route for glucose, lactate, urea, ketone, and peripheral hypoxanthine sensing. Translational value depends on enzyme preservation, diffusion control, oxygen dependence, and interference suppression.[4,10,15,21,22,23,24,77,94,101]
Nanozyme and nonenzymatic catalytic interfacesInorganic or hybrid catalysts replace or supplement natural enzymes and generate electrochemical or colorimetric outputs.These interfaces are useful where enzyme stability is limiting, but catalytic response should not be treated as molecularly specific unless interference and matrix effects are clearly controlled.[12,50,58,63,80,88,102]
Aptamer, antibody, immunoassay, and MIPsAffinity receptors enable detection of drugs, hormones, proteins, cytokines, and non-redox-active analytes.This category provides the most important bridge from biosensing to therapeutic monitoring. Remaining concerns include receptor drift, nonspecific binding, protein fouling, and stability in swollen hydrogels.[18,25,26,28,29,30,31,33,70,103]
Nucleic acid and CRISPR-enabled recognitionProbe DNA, DNA-gated MOFs, graphene biointerfaces, and CRISPR-associated systems enable sequence-specific detection.This strategy expands HFMNs, HMNs, and related microneedle platforms toward infectious, genetic, and prognostic biomarkers, but probe retention, nuclease resistance, and hydrated-matrix interference remain key translational uncertainties.[20,53,65,78,97]
Conductive and antifouling transducer architecturesCNTs, graphene, MXene, PEDOT:PSS, nanostructured electrodes, chitosan, Nafion, zwitterionic hydrogels, and protective cavities improve signal transfer and interface durability.Continuous sensing is limited as much by fouling, drifting, delamination, abrasion, and contact instability as by receptor chemistry. Comparative long-term skin compatibility of conductive fillers remains insufficiently resolved.[8,40,44,52,67,83,93,96,106,114]
Ion, pH, oxygen, and contextual sensingPotentiometric, redox, conductive-polymer, and electrolyte-gel interfaces measure local physiological context in ISF, skin, subcutaneous, or comparator settings.These signals are essential for interpreting wounds, inflammation, and treatment response, but they are vulnerable to local pH heterogeneity, ionic variation, biofilms, and exudate composition.[5,7,8,55,59,62,72,76,107,108]
Optical, SERS, fluorescence, and plasmonic transductionPlasmonic substrates, SERS probes, photonic hydrogels, fluorescence probes, localized surface plasmon resonance (LSPR), and metal-enhanced fluorescence (MEF) interfaces convert recognition into spectral or visual outputs.These approaches are valuable for multiplexing and molecular fingerprinting. Key unresolved issues include optical calibration, spectral overlap, nonspecific adsorption, probe stability, and swelling-induced signal variation.[39,46,47,54,69,109,110,111,112,113]
Multiplexed or multi-parameter therapeutic-monitoring architecturesSpatial separation, independent electrodes, hydrophobic barriers, parallel modules, and multimodal outputs enable multi-analyte or treatment-relevant panels.The field is progressing toward therapeutically actionable monitoring, but multiplexed systems must prove cross-reactivity control, calibration stability, drift resistance, and compatibility with drug-delivery functions.[8,16,21,28,41,55,61,90,105,112]
Table 4. Analytical benchmarks and reliability criteria most relevant to HFMNs for ISF biosensing and therapeutic monitoring.
Analytical Performance, Benchmarking, and Wear-Associated Failure ModesKey EvidenceEvidence ShowsTranslational ImplicationReferences
Biologically matched operating rangeGlucose ranges include 1–30 mM, 4–24 mM, 1.5–14 mM, and linearity up to 35 mM; urea spans 3–18 mM; uric acid includes 150–500 µM and wider 1–800 µM or 5–600 µM ranges; ions cover sodium ions from 0.75–200 mM, potassium ions from 1–128 mM, calcium ions from 0.25–4.25 mM, and pH from 5.5–8.5.The strongest systems match the expected biological or therapeutic window rather than simply reporting low limits of detection (LODs).Range relevance is a primary acceptance criterion for monitoring enabled by HFMNs.[7,12,15,24,61,83,85,95,105,119]
ISF sampling as an analytical variableSampling metrics include approximately 2 µL per needle per hour, 5.6 µL in 5 min, 60.2 mg in 10 min, approximately 6.87 µL per needle in 5 min, and extraction comparable to negative-pressure collectors; reverse iontophoresis increased glucose flux by approximately 1.6-fold.Fluid uptake, swelling, and extraction kinetics affect calibration, lag, and matrix agreement.Sampling performance in HFMNs and related ISF-accessing microneedles should be reported alongside sensor metrics, not treated as a separate design feature.[7,11,17,45,60,80]
Temporal behavior and monitoring durationReported values include 2–3 s glucose response, approximately 95 s in vivo glucose response, approximately 2 min skin-model lag, approximately 10 min physiological blood lag, 8 s lactate response, 1–4 h cytokine response, and 20 min phenylalanine lag; stability spans days to weeks depending on the platform.Continuous monitoring requires known response kinetics and operational stability.Single-point sensitivity cannot establish therapeutic-monitoring readiness.[10,12,14,15,23,24,27,34,40,117]
Comparator and matrix benchmarkingGlucose correlates with commercial glucometers or blood; one SERS glucose system placed 93% of values in Clarke error grid zones A and B. Antibiotic monitoring correlated with blood for vancomycin, gentamicin, and tobramycin. Methylene blue showed comparable ISF–blood levels, whereas mitoxantrone was 2–3 orders of magnitude lower in ISF. Cortisol matched ELISA or blood trends.ISF is informative, but blood equivalence is analyte dependent.Therapeutic monitoring requires analyte-specific ISF–blood or reference-method validation.[10,11,13,15,28,29,31,39,54,64]
Selectivity and multiplex interference controlGlucose sensors minimized interference from ascorbic acid, uric acid, acetaminophen, mannose, and other electroactive species; uric acid/dopamine systems tolerated ascorbic acid; cortisol, IgE, cytokine, endotoxin, bacterial, and CRISPR systems reported high specificity.Cross-reactivity and matrix effects are key barriers, particularly in multiplexed or protein-rich ISF environments.Selectivity should be interpreted under realistic matrix and wear conditions, not only in simple buffers.[22,26,34,46,53,64,66,105,117,119]
Wear-associated failure modesEvidence includes reduced delamination and biofouling, protective films against proteins and cells, antifouling or antimicrobial sensing, 8.4% signal decrease after four insertions, <3.3% calibration difference during piercing, 5.8% on-body signal difference, magnetic stabilization against sensor push-out, and 6-day abrasion-immune in vivo lifetime.Wear reliability is less consistently quantified than analytical sensitivity.Biofouling, drift, insertion damage, and contact loss are central barriers to translation of HFMNs.[40,52,67,83,90,93,94,95,96,106]
Macromolecular and pathogen monitoringIgG LOD of 0.05 ng/mL; IgE LOD of 30.6 pg/mL over 88 pg/mL–100 ng/mL; human epidermal growth factor receptor 2 and CEA detection reached ng/mL-level limits; S100B, IL-6, IFN-α, and cytokine-storm markers reached pg/mL-level detection; bacteria were captured within 5 min with >50% efficiency and 97.87% classification accuracy.Sensitivity is strong, but drift, repeated-wear stability, and matrix robustness remain unevenly reported.These platforms expand HFMN-compatible and microneedle-enabled sensing toward immune, infection, cancer/prognostic, and pathogen monitoring, but they require stronger continuous-use validation.[17,26,32,34,35,46,56,103,115]
Non-clinical comparator evidenceA fish-tissue hypoxanthine microneedle biosensor detected hypoxanthine over 5–50 and 50–200 µM, with 0.024 µA/µM sensitivity, 2.18 ± 0.75 µM LOD, approximately 100 s response, interference tolerance, and agreement with a commercial Amplex Red assay over 48 h.Non-clinical systems demonstrate direct-sample electrochemical benchmarking and comparator validation.These studies are useful as methodological context but should not be used as evidence for dermal ISF performance.[77]
Table 5. Hydrogel-forming and hydrogel-assisted microneedle platforms across validation readiness and therapeutic-monitoring translation.
Validation Stage, Translational Readiness, and Closed-Loop or Drug-Delivery ImplicationsEvidence PatternMost Relevant Validation SignalCritical InterpretationReferences
Early ISF biosensing feasibilityHydrogel, swellable, porous, or hydrogel-coated systems establish ISF extraction and on-patch detection mainly in artificial ISF, phantoms, ex vivo models, or small animals.Examples include 14-day repeatability with RSD < 4%, 60.2 mg ISF extraction within 10 min in vitro, porous microneedle detection, and SERS-based molecular sensing.These studies prove technical feasibility, not clinical readiness; they require comparator alignment, realistic wear testing, and human-relevant safety evidence.[22,66,80,112,113]
Early human or multi-species hydrogel microneedle validationA limited subset has moved toward human or multi-species validation.Hydrogel-microneedle ketone monitoring was tested in rats, swine, and pilot human participants; swellable ion sensing was tested in mice, humans, and plants with approximately 6.87 µL per needle extraction in 5 min.These studies are important translational bridges, but human evidence remains early and should not be generalized across analytes or devices.[7,19]
Comparator-aligned clinical interpretationThe strongest studies compare ISF readouts with blood, ELISA, conventional probes, LC–MS, or treatment-response context.A flexible hydrogel-microneedle antibiotic platform correlated antibiotic profiles with blood measurements; the integrated ultraswelling microneedle aptamer-recognition tester (uSMART) provided CRP tracking during MRSA infection and vancomycin treatment; hydrogel microneedle pH sensing reached 93% accuracy versus a conventional probe.Comparator alignment is essential because ISF–blood relationships are analyte- and drug-dependent.[5,28,30,31,39,40]
Wearability, durability, and skin-interface safetyWearable claims are supported by wireless readout, multi-day operation, biosafety, antimicrobial features, or limited post-use skin observations.Evidence includes cytocompatibility, antimicrobial wound functions, biosafety, absence of significant tissue damage in selected systems, one 10 min skin-recovery report outside the HFMN subset, and quantified insertion robustness.Safety evidence is promising but fragmented; repeated insertion, prolonged wear, irritation, inflammation, and infection risk remain insufficiently resolved.[8,20,41,44,54,95,115]
Sterilization, antifouling, and quality readinessFew studies directly address sterilization or fouling under clinically relevant conditions.A zwitterionic hydrogel insulin patch tolerated UV crosslinking and FDA-standard gamma irradiation; core–shell zwitterionic hydrogel microneedles showed antifouling behavior and biosafety; a commercial off-the-shelf (COTS) comparator used sterilizable microneedles.These are isolated readiness signals; broader validation must test sterilization effects on swelling, mechanics, diffusion, and biosensor function.[18,44,116]
Therapeutic monitoring and treatment-response trackingDrug, infection, cytokine, and pharmacokinetic platforms shift the field from detection toward decision support.Antibiotic monitoring, CRP tracking during MRSA infection and vancomycin treatment, drug pharmacokinetics, fentanyl extraction, organ-function monitoring, and regenerable aptameric sensing provide feedback-relevant evidence.These platforms support therapeutic monitoring, but not autonomous therapy. Clinical value must be shown through dosing accuracy, toxicity reduction, or response endpoints.[6,28,29,30,39,40,70]
Delivery-capable and theranostic systemsA small subset integrates sensing with drug delivery, insulin delivery, wound therapy, or electrical stimulation.Methotrexate sensing was paired with iontophoretic delivery; an HFMN wound dressing monitored seven biomarkers and accelerated wound closure; MN-TENG combined antibiotic release, stimulation, and sensing; a diabetic microneedle theranostic platform (MNTP) combined sensing with insulin delivery.These systems approach monitoring–delivery integration, but none proves sensor-output-controlled dosing or closed-loop actuation.[8,41,42,67]
Manufacturing and regulatory-readiness gapFabrication is increasingly scalable, but regulatory-grade production evidence is limited.Low-cost 3D printing, laser-based fabrication, mold-based fabrication, clinical-grade needle conversion, and scalable approaches based on MIPs are reported.Translation now depends less on whether devices can be made and more on reproducibility, sterilization, storage, standardized testing, and quality-by-design controls.[1,2,3,29,58,84,87,89,92,103]
Table 6. Evidence-to-Practice Roadmap for Hydrogel-Forming Microneedles in Interstitial-Fluid Biosensing and Therapeutic Monitoring.
Roadmap StageCurrent Evidence SupportsKey UncertaintyPractice InterpretationFuture Priority
RationaleHFMNs and hydrogel-integrated platforms can access ISF and monitor clinically relevant metabolites, ions, proteins, nucleic acids, wound biomarkers, microbial targets, and therapeutic drugs [6,7,8,16,18,19,20,28,30,46].Whether ISF readouts consistently add clinical value beyond blood, urine, sweat, or existing wearable monitoring.HFMNs should be positioned as minimally invasive biochemical access platforms, not universal replacements for blood-based testing.Define use cases in which continuous or frequent ISF monitoring changes management, including antibiotic dosing, ketoacidosis risk, wound deterioration, drug clearance, or treatment-response tracking.
MechanismHydrated or swellable polymer networks support skin interfacing, ISF uptake, analyte diffusion, and integration with electrochemical, optical, aptameric, enzymatic, immunochemical, and conductive sensing layers [4,5,6,7,8,18,30,31,44,78].How hydrogel swelling, crosslinking, conductivity, receptor stability, and diffusion control interact during prolonged wear.Mechanistic claims should link hydrogel structure to clinical sensing function, not merely report detection in artificial matrices.Establish minimum reporting standards for insertion force, swelling ratio, ISF uptake, analyte diffusion, sensor drift, skin recovery, and post-sterilization performance.
Evidence baseThe strongest evidence supports feasibility and preclinical monitoring; human-facing validation exists but remains limited for phenylalanine, cortisol, glucose, ketones, and ions [7,14,19,27,64].Generalizability across skin types, disease states, wear durations, patient ages, comorbidities, and medication regimens.Current evidence justifies translational development and targeted pilot studies, but not broad clinical implementation.Move from artificial ISF and animal models to prospective human studies with predefined accuracy, usability, safety, and decision-impact endpoints.
Populations and contextsThe most plausible near-term contexts are conditions in which frequent biochemical information could improve management: diabetes, infection, antibiotic therapy, wound care, organ-function-related drug clearance, and narrow-therapeutic-index pharmacotherapy [8,19,28,29,30,40,41,42,67].Which patients benefit most, including high-risk inpatients, outpatient chronic-disease populations, wound-care patients, pediatric or geriatric groups, and individuals with poor venous access.Adoption should begin in clinically constrained scenarios in which current sampling is burdensome, delayed, or insufficiently continuous.Prioritize context-specific trials, including antibiotic therapeutic drug monitoring (TDM) in high-risk patients, wound-response monitoring in chronic wounds, ketone monitoring in diabetes, and drug-clearance monitoring in renal or hepatic impairment.
OutcomesExisting studies support biomarker detection, pharmacokinetic profiling, treatment-response monitoring, and selected theranostic functions [1,2,8,28,29,30,39,40,41,67].Whether measured signals improve patient-centered outcomes rather than only analytical performance.Clinical value should be judged by measurable endpoints, not detection limits alone.Define endpoints prospectively: dosing accuracy by time in therapeutic range, dose-adjustment error, or agreement with reference TDM; toxicity reduction by nephrotoxicity, ototoxicity, hypoglycemia, local irritation, infection, or adverse drug events; treatment-response improvement by CRP decline, pathogen control, wound-closure rate, glycemic stabilization, ketoacidosis prevention, or reduced treatment failure; usability and adherence by wear time, successful-use rate, comfort, pain scores, and missed-sample reduction; and cost-effectiveness by cost per actionable result, avoided blood draws, reduced clinic visits, shorter hospitalization, prevented adverse events, or cost per quality-adjusted life-year.
Practice and implementationWearable readout, wireless transmission, AI-assisted short-term forecasting, abnormal-signal alerts, antimicrobial designs, and selected sterilization-compatible systems indicate practical potential [1,3,18,30,36,37,48,116,119].Whether devices can meet regulatory-grade reliability, manufacturing reproducibility, sterilization compatibility, data security, workflow integration, and reimbursement requirements.HFMNs should first be implemented as decision-support tools under clinician oversight, especially where dosing or treatment decisions carry safety risks.Develop implementation studies that test device training, data interpretation, alert thresholds, clinician response protocols, electronic-record integration, patient acceptance, and health-economic impact.
Future gapsThe field has progressed from ISF access to therapeutic monitoring and early theranostic prototypes, including methotrexate monitoring/delivery, wound-management systems, antibiotic-release/stimulation platforms, and diabetes theranostics [8,41,42,67].True autonomous closed-loop control remains insufficiently demonstrated; most platforms do not prove sensor-output-controlled dosing, release, or therapeutic adjustment.Closed-loop terminology should be reserved for systems in which sensor output demonstrably governs an actuator, dose, or treatment decision with validated safety controls.Establish staged translation: analytical validation → ISF/reference correlation → clinical decision thresholds → supervised dose adjustment → safety-locked feedback control → outcome and cost-effectiveness trials.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.