1. Introduction
Thoracic kyphosis, quantified by the Cobb angle on standing lateral X-rays [
1], is associated with impaired mobility, pulmonary restriction, pain, and increased vertebral fracture risk in older adults [
2]. Accurate measurement of the Cobb angle, however, can be challenging [
3,
4,
5]. In younger, flexible spines, standing radiographs may yield a wide range of values depending on patient positioning [
6]. A diurnal variation has been reported [
6], with standing kyphosis increasing by approximately 5° between same-day morning and evening radiographs, presumably due to fatigue. Interestingly, there is minimal difference in Cobb angles between standing and supine positioning in older patients [
7], and CT performed with supine positioning has been used for Cobb angle measurements [
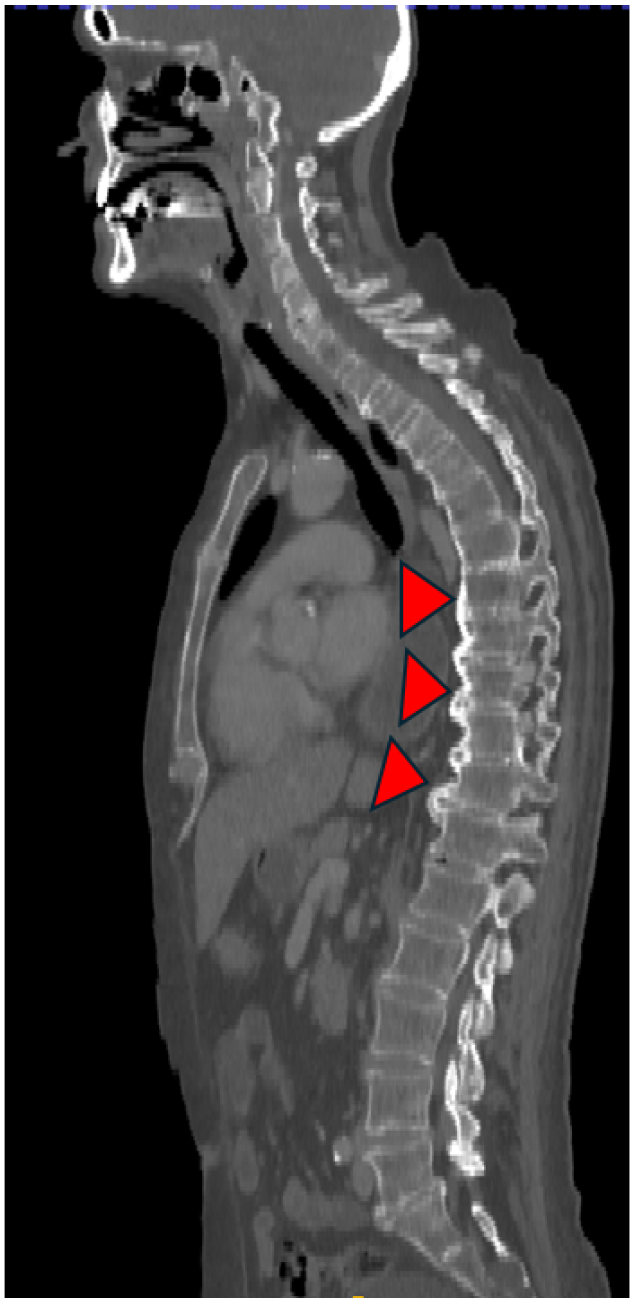
2]. Although a normal spine may straighten in the supine position, a spine habituated to thoracic kyphosis may not fully straighten even when lying supine; see
Figure A1, which shows ossification of the anterior longitudinal ligament preventing dorsiflexion of the thoracic spine. Thus, supine CT may have less postural bias compared to standing X-rays for assessing the degree to which a patient can relax into normal spinal alignment [
2,
7]. Although manual Cobb angle measurements on CT can be performed with good reproducibility following appropriate training, it remains labor-intensive and reader-dependent, and is therefore underutilized in routine clinical practice [
3,
4,
5]. Automated or surrogate biomarkers could improve throughput and enable opportunistic screening of sagittal deformity and identification of patients who may benefit from intervention.
Muscle composition analysis on CT offers a quantitative framework for assessing musculoskeletal health [
2,
8,
9,
10]. CT can quantify both muscle volume and intramuscular fat [
2,
9,
10]. Intramuscular fat develops through both lipid accumulation within myocytes and expansion of intramuscular adipocytes [
8]. Sarcopenia, the age-related loss of skeletal muscle mass and function, is associated with progressive reductions in muscle quantity and deterioration in muscle quality through fatty infiltration [
8,
11]. Muscle mass has been reported to decline by approximately 3% to 8% per decade after the age of 30, with faster decline at older ages [
11].
In this study, muscle–fat% is defined as the percentage of voxels within each segmented muscle with attenuation below
HU, and is used as a quantitative marker of intramuscular fatty atrophy and muscle decline with aging, inactivity, or chronic spine pathology [
2,
10,
12].
Elevated muscle–fat% in paraspinal and trunk muscles has been associated with reduced strength, imbalance, and deformity progression in lumbar and cervical regions [
10,
12,
13,
14,
15,
16,
17]. However, the relationship between CT-derived muscle–fat% of thoracic or trunk musculature and thoracic kyphosis in supine position remains incompletely characterized. Establishing this link could clarify how muscular degeneration with fatty atrophy contributes to structural curvature and functional impairment.
Building on these insights, we propose an automated, reproducible pipeline for thoracic alignment analysis that integrates manual and deep learning-based muscle segmentation with voxelwise quantification of muscle–fat% [
2,
18]. Muscle volume is directly measured from the segmentation volumes. Muscle–fat% is measured by counting intramuscular voxels with attenuation below
HU [
2,
10].
Using the AtlasDataset [
19,
20], we first validated inter-observer variability of manual Cobb angle measurements [
21] from the CT scans. Cobb angle measurements from the multiple observers were then averaged to create the reference standard for the supine thoracic kyphosis. Then we trained an nnU-Net segmentation model [
18] to segment and compute muscle–fat% across nine bilateral muscle groups in the entire 533-case CT cohort. The segmentation model was validated in another CT dataset [
22]. We next tested correlations between muscle–fat% and supine thoracic curvature to determine whether muscle fatty atrophy is associated with increased supine kyphotic deformity. Our overarching aim is to evaluate muscle–fat% as a scalable surrogate of spinal curvature—providing quantitative, opportunistic assessment of supine kyphosis on routine CT scans [
2].
This integrated framework supports reproducible measurement of spinal alignment and muscle composition, bridging radiological and biomechanical markers of sagittal imbalance while laying groundwork for population-scale, AI-assisted spine health analytics.
2. Materials and Methods
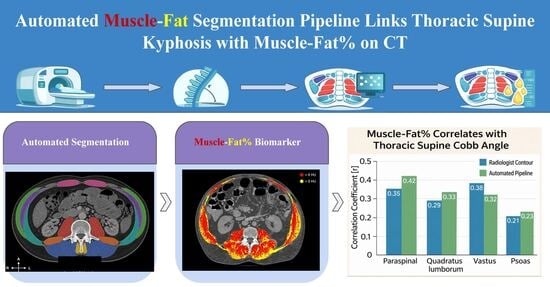
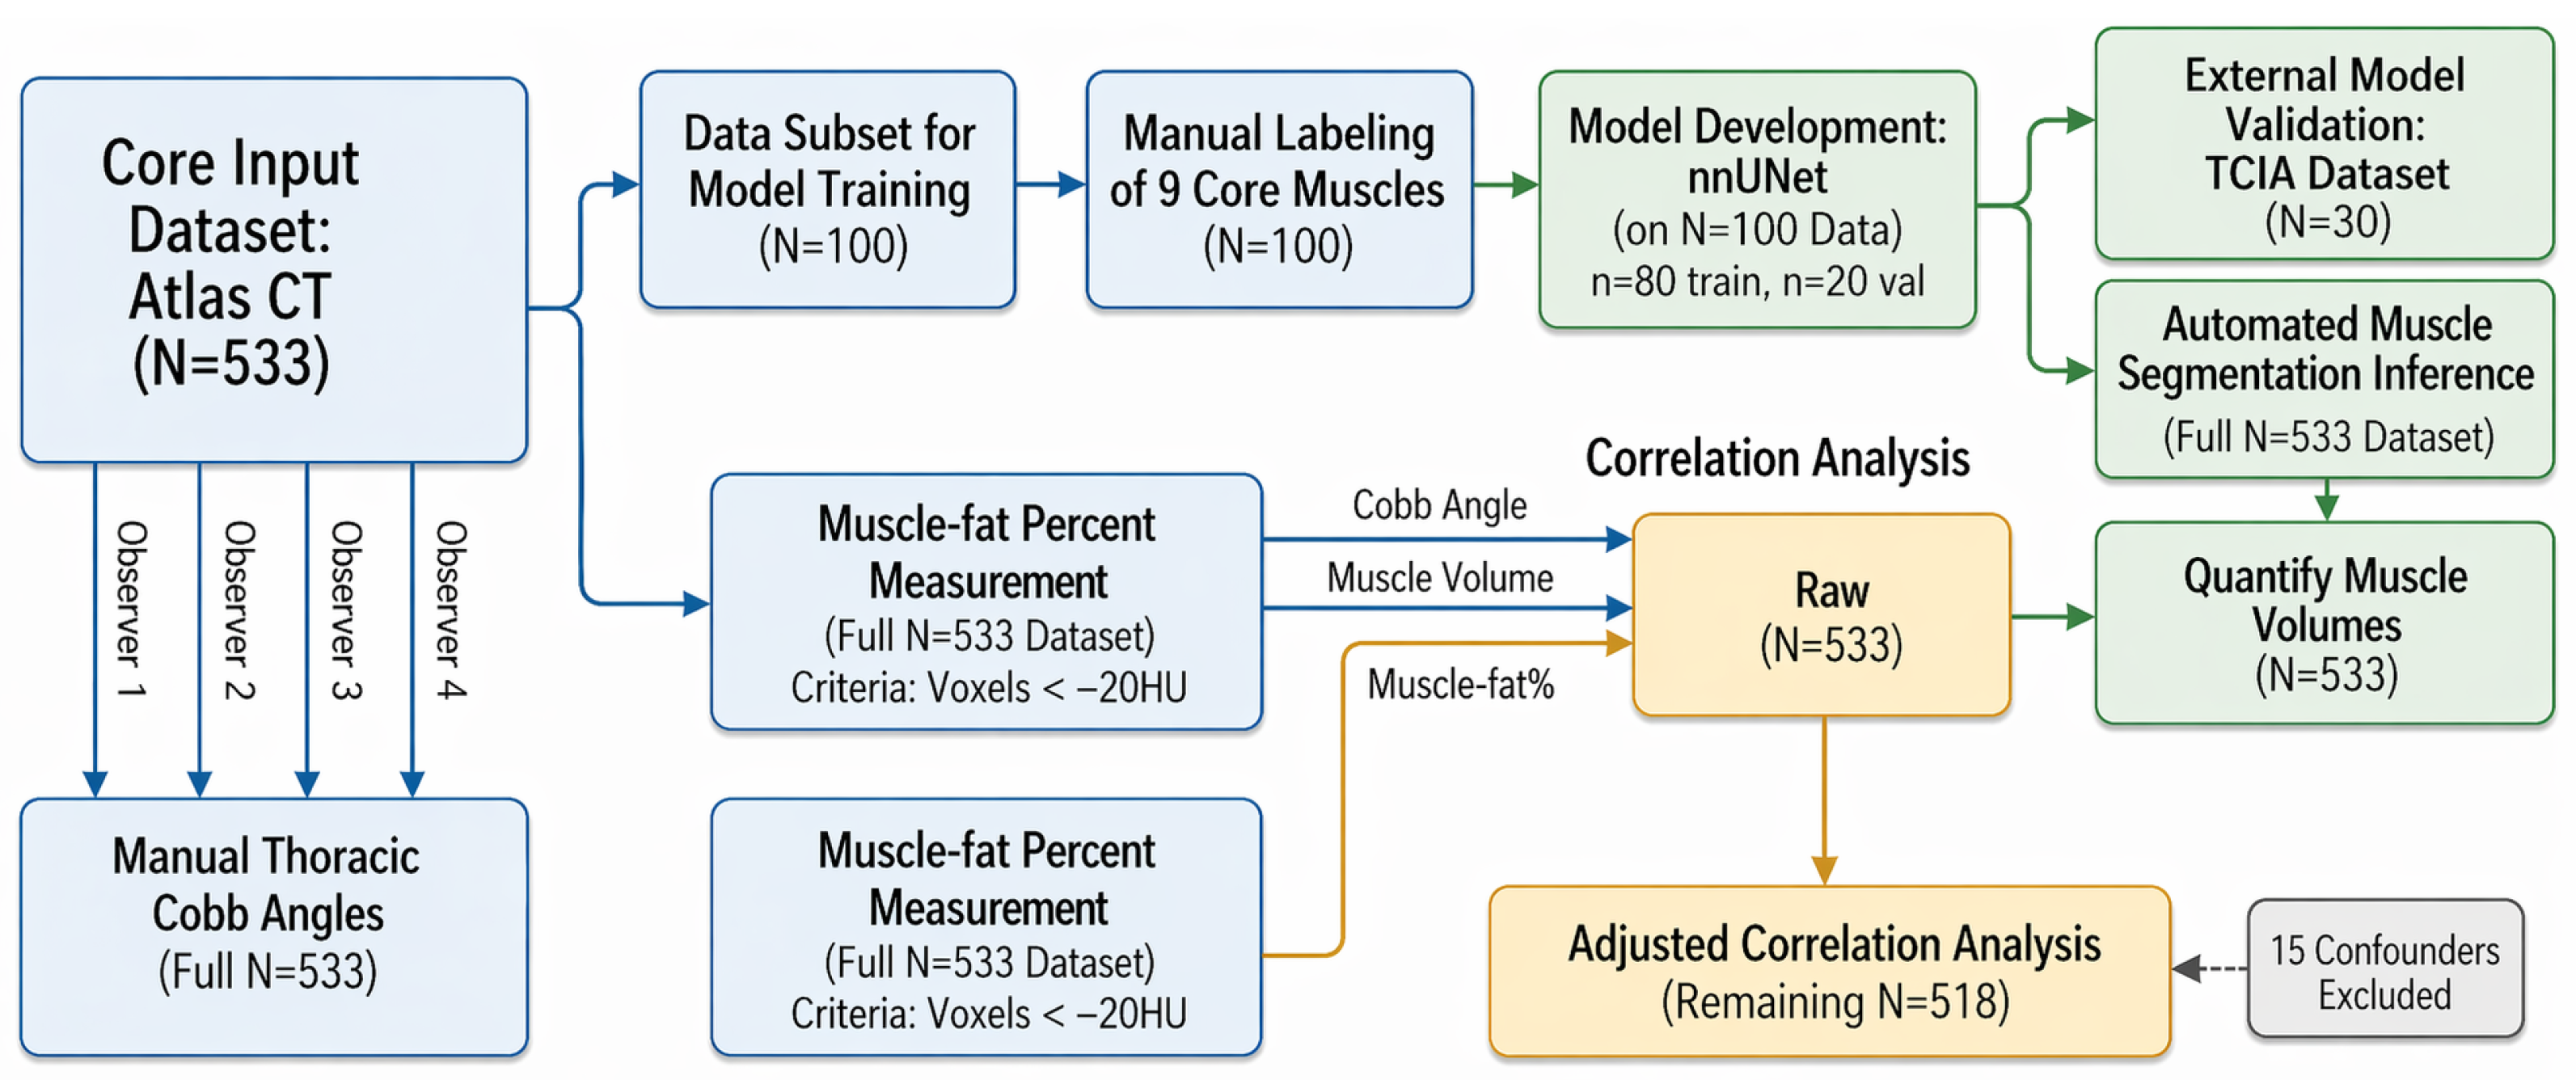
An overview of the full study workflow is shown in
Figure 1, including AtlasDataset case selection, manual thoracic supine Cobb angle measurement, manual muscle segmentation for nnU-Net development, external segmentation benchmarking, automated muscle–fat% quantification, confounder exclusion, and downstream correlation analysis between muscle–fat% and thoracic supine kyphosis.
2.1. Dataset and Manual Thoracic Supine Kyphosis on CT
We utilized de-identified adult whole-body CT volumes from the AtlasDataset [
19,
20], a publicly available resource providing high-resolution, label-rich imaging suitable for anatomical measurement and deep learning-based model development. A separate external cohort of CT scans was obtained from The Cancer Imaging Archive (TCIA) CT-ORG collection for independent segmentation performance evaluation [
22]. For external segmentation benchmarking, trunk muscles were manually segmented on a subset of the external cohort (
) using the same label taxonomy and protocol as AtlasDataset, enabling Dice-based performance evaluation.
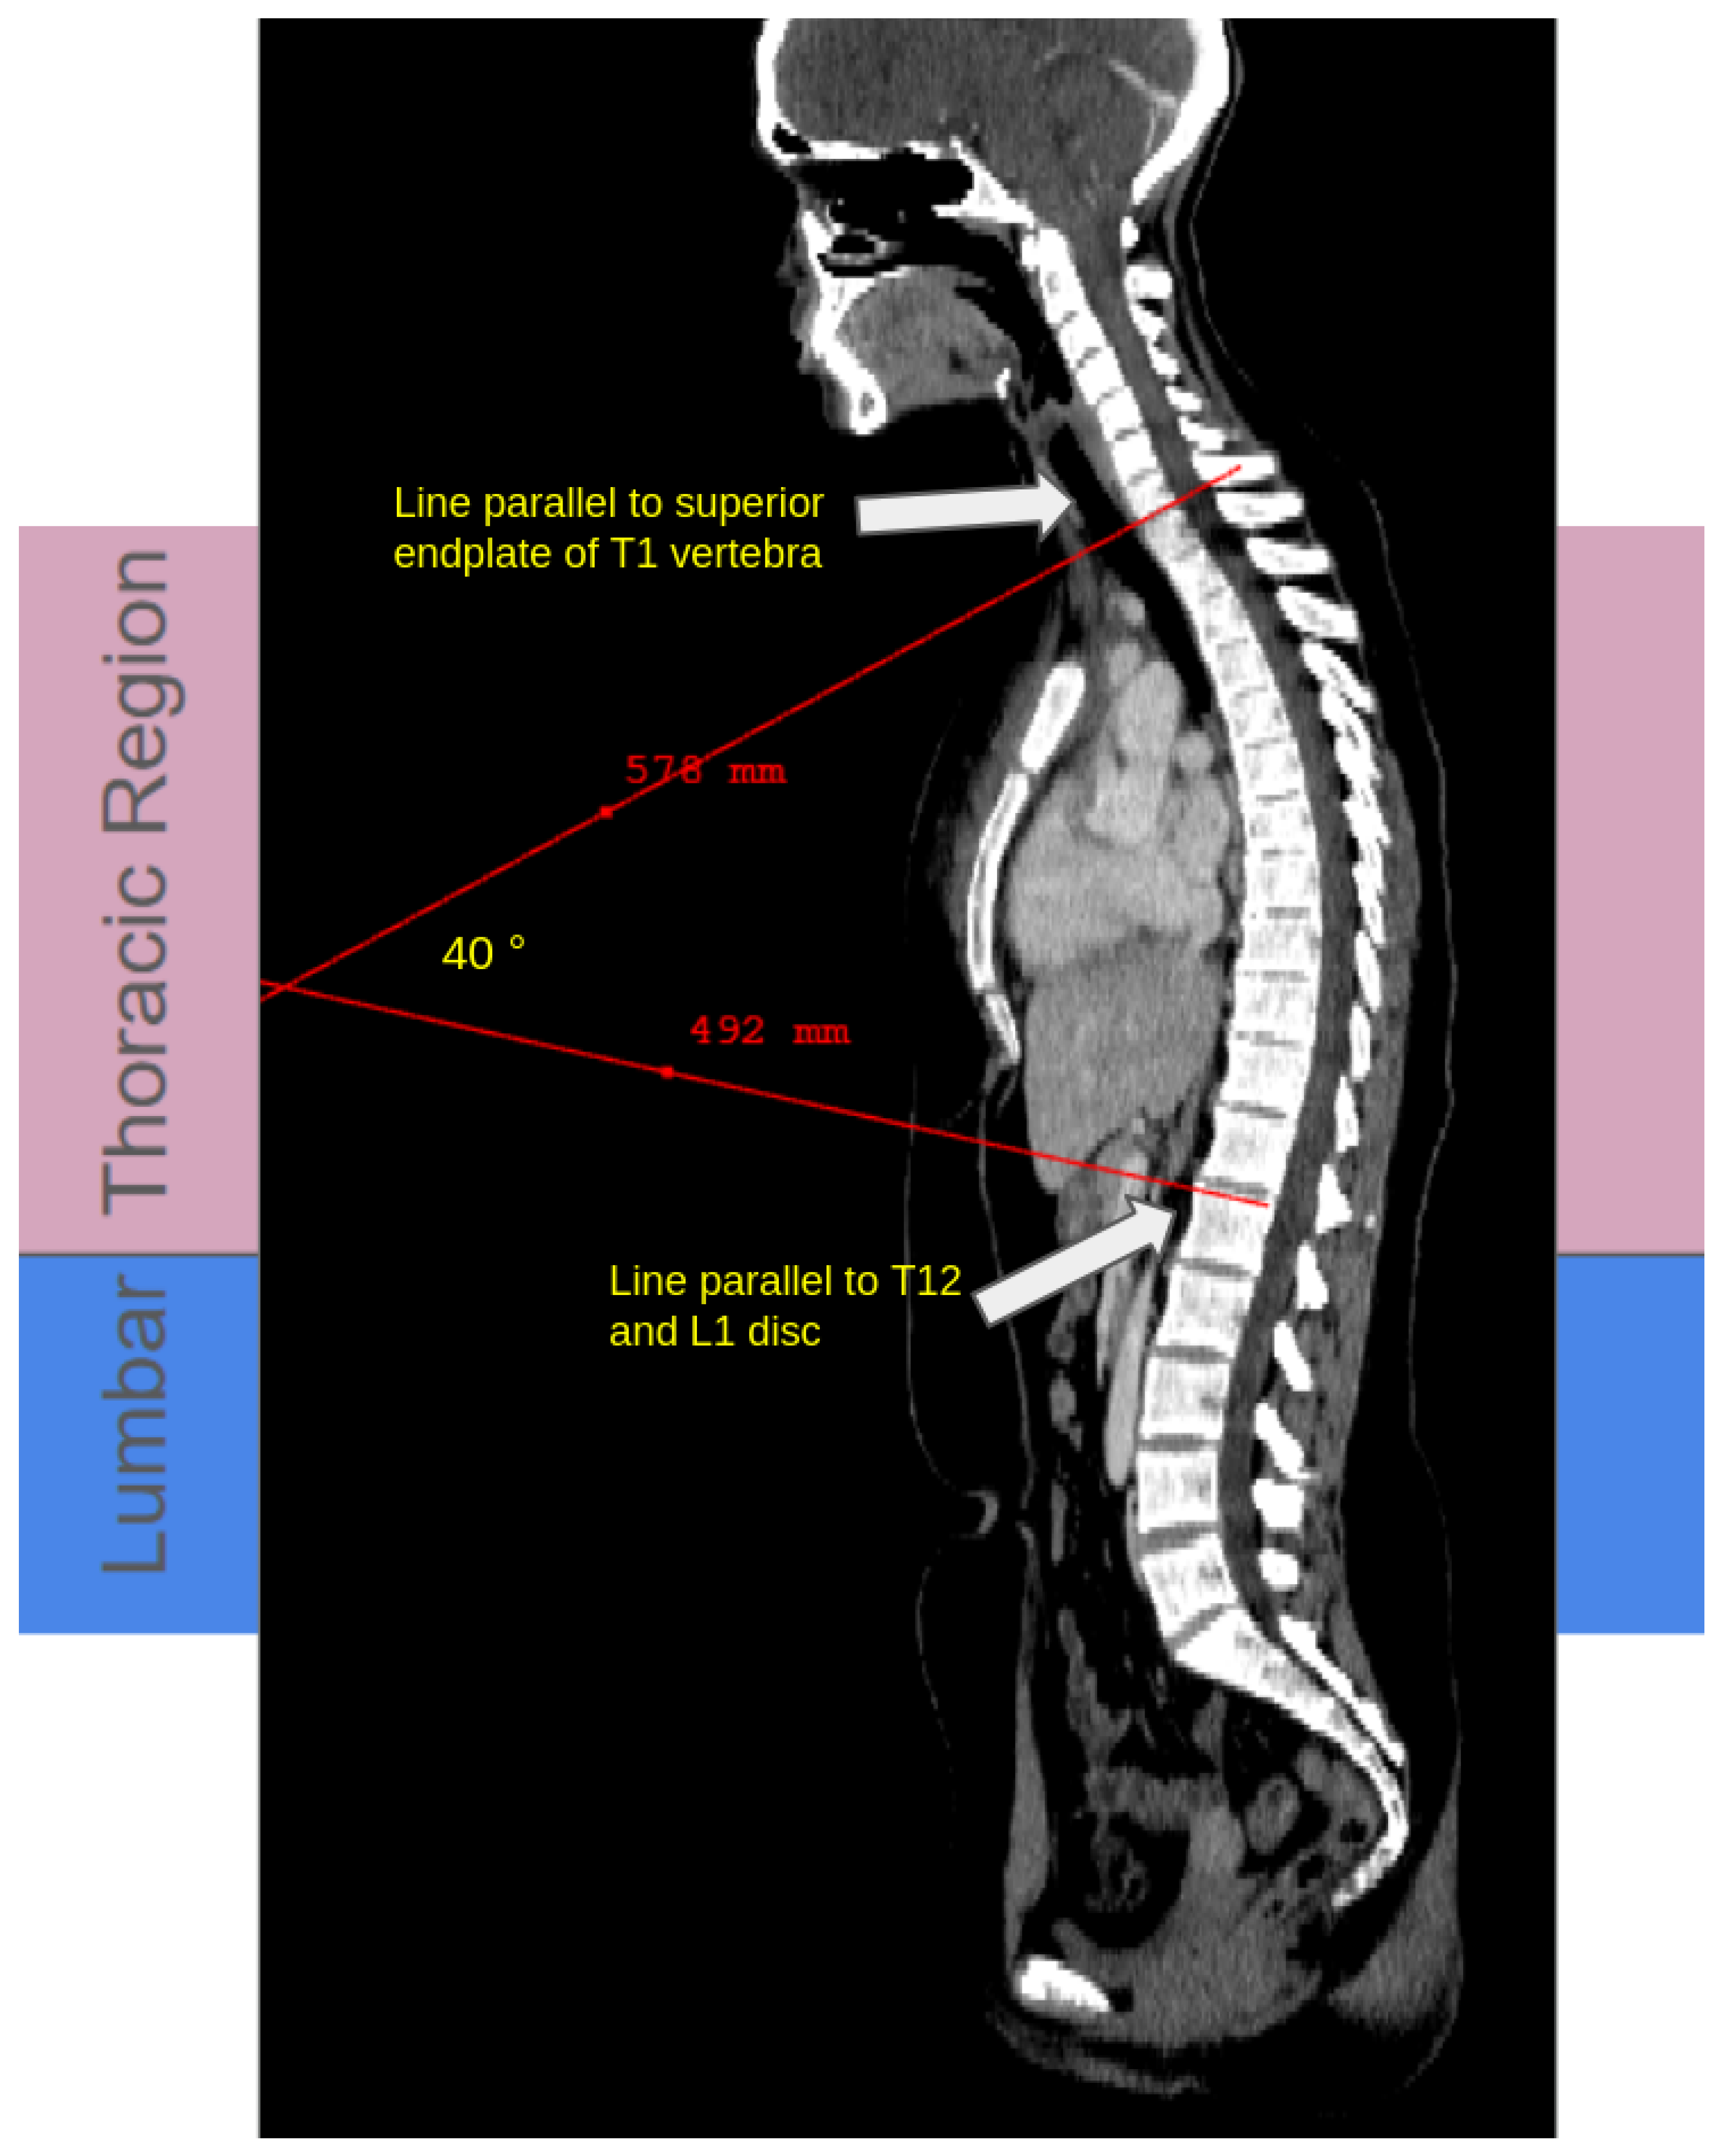
Thoracic supine kyphosis was quantified using the Cobb angle measured on mid-sagittal CT reconstructions, defined between the superior endplate of T1 and the inferior endplate of T12/L1, following standard radiographic conventions (
Figure 2) [
1].
2.1.1. ManualCobb Angle Measurement and Reliability
Supine thoracic Cobb angles for all cases included in this study were independently measured by four trained observers in all 533 cases. Inter-observer agreement was quantified using the two-way random-effects intraclass correlation coefficient (ICC(2,
k)) with absolute agreement and bootstrap 95% confidence intervals [
21]. For all subsequent analyses, the mean Cobb angle across the four observers was used as the reference value.
2.1.2. nnU-Net Segmentation Benchmark
For segmentation model development and benchmarking, 100 manually labeled AtlasDataset scans were partitioned at the subject level into 80 cases for nnU-Net training and 20 cases for internal validation. An independent external segmentation benchmarking cohort () was used exclusively for segmentation performance evaluation. The internal validation set was used solely for monitoring convergence and model selection and was not used for final benchmarking.
2.1.3. Muscle–Fat% Quantification and Correlation Analysis
For biomarker analysis, intramuscular fat percentage (muscle–fat%) was computed within muscle segmentations and correlated with supine thoracic Cobb angle using Pearson’s correlation. Correlations were computed in AtlasDataset only using two cohorts: (i) the manual cohort () with manual muscle segmentations, and (ii) the automated cohort () segmented using the trained nnU-Net model.
2.2. Confounder Identification and Exclusion
To assess robustness of associations between thoracic supine kyphosis and muscle–fat percentage, cases were screened for predefined confounders expected to disrupt the biomechanical relationship between upright posture and trunk muscle composition. These included prior spine surgery and profound fatty muscle atrophy (paraspinal muscle–fat%
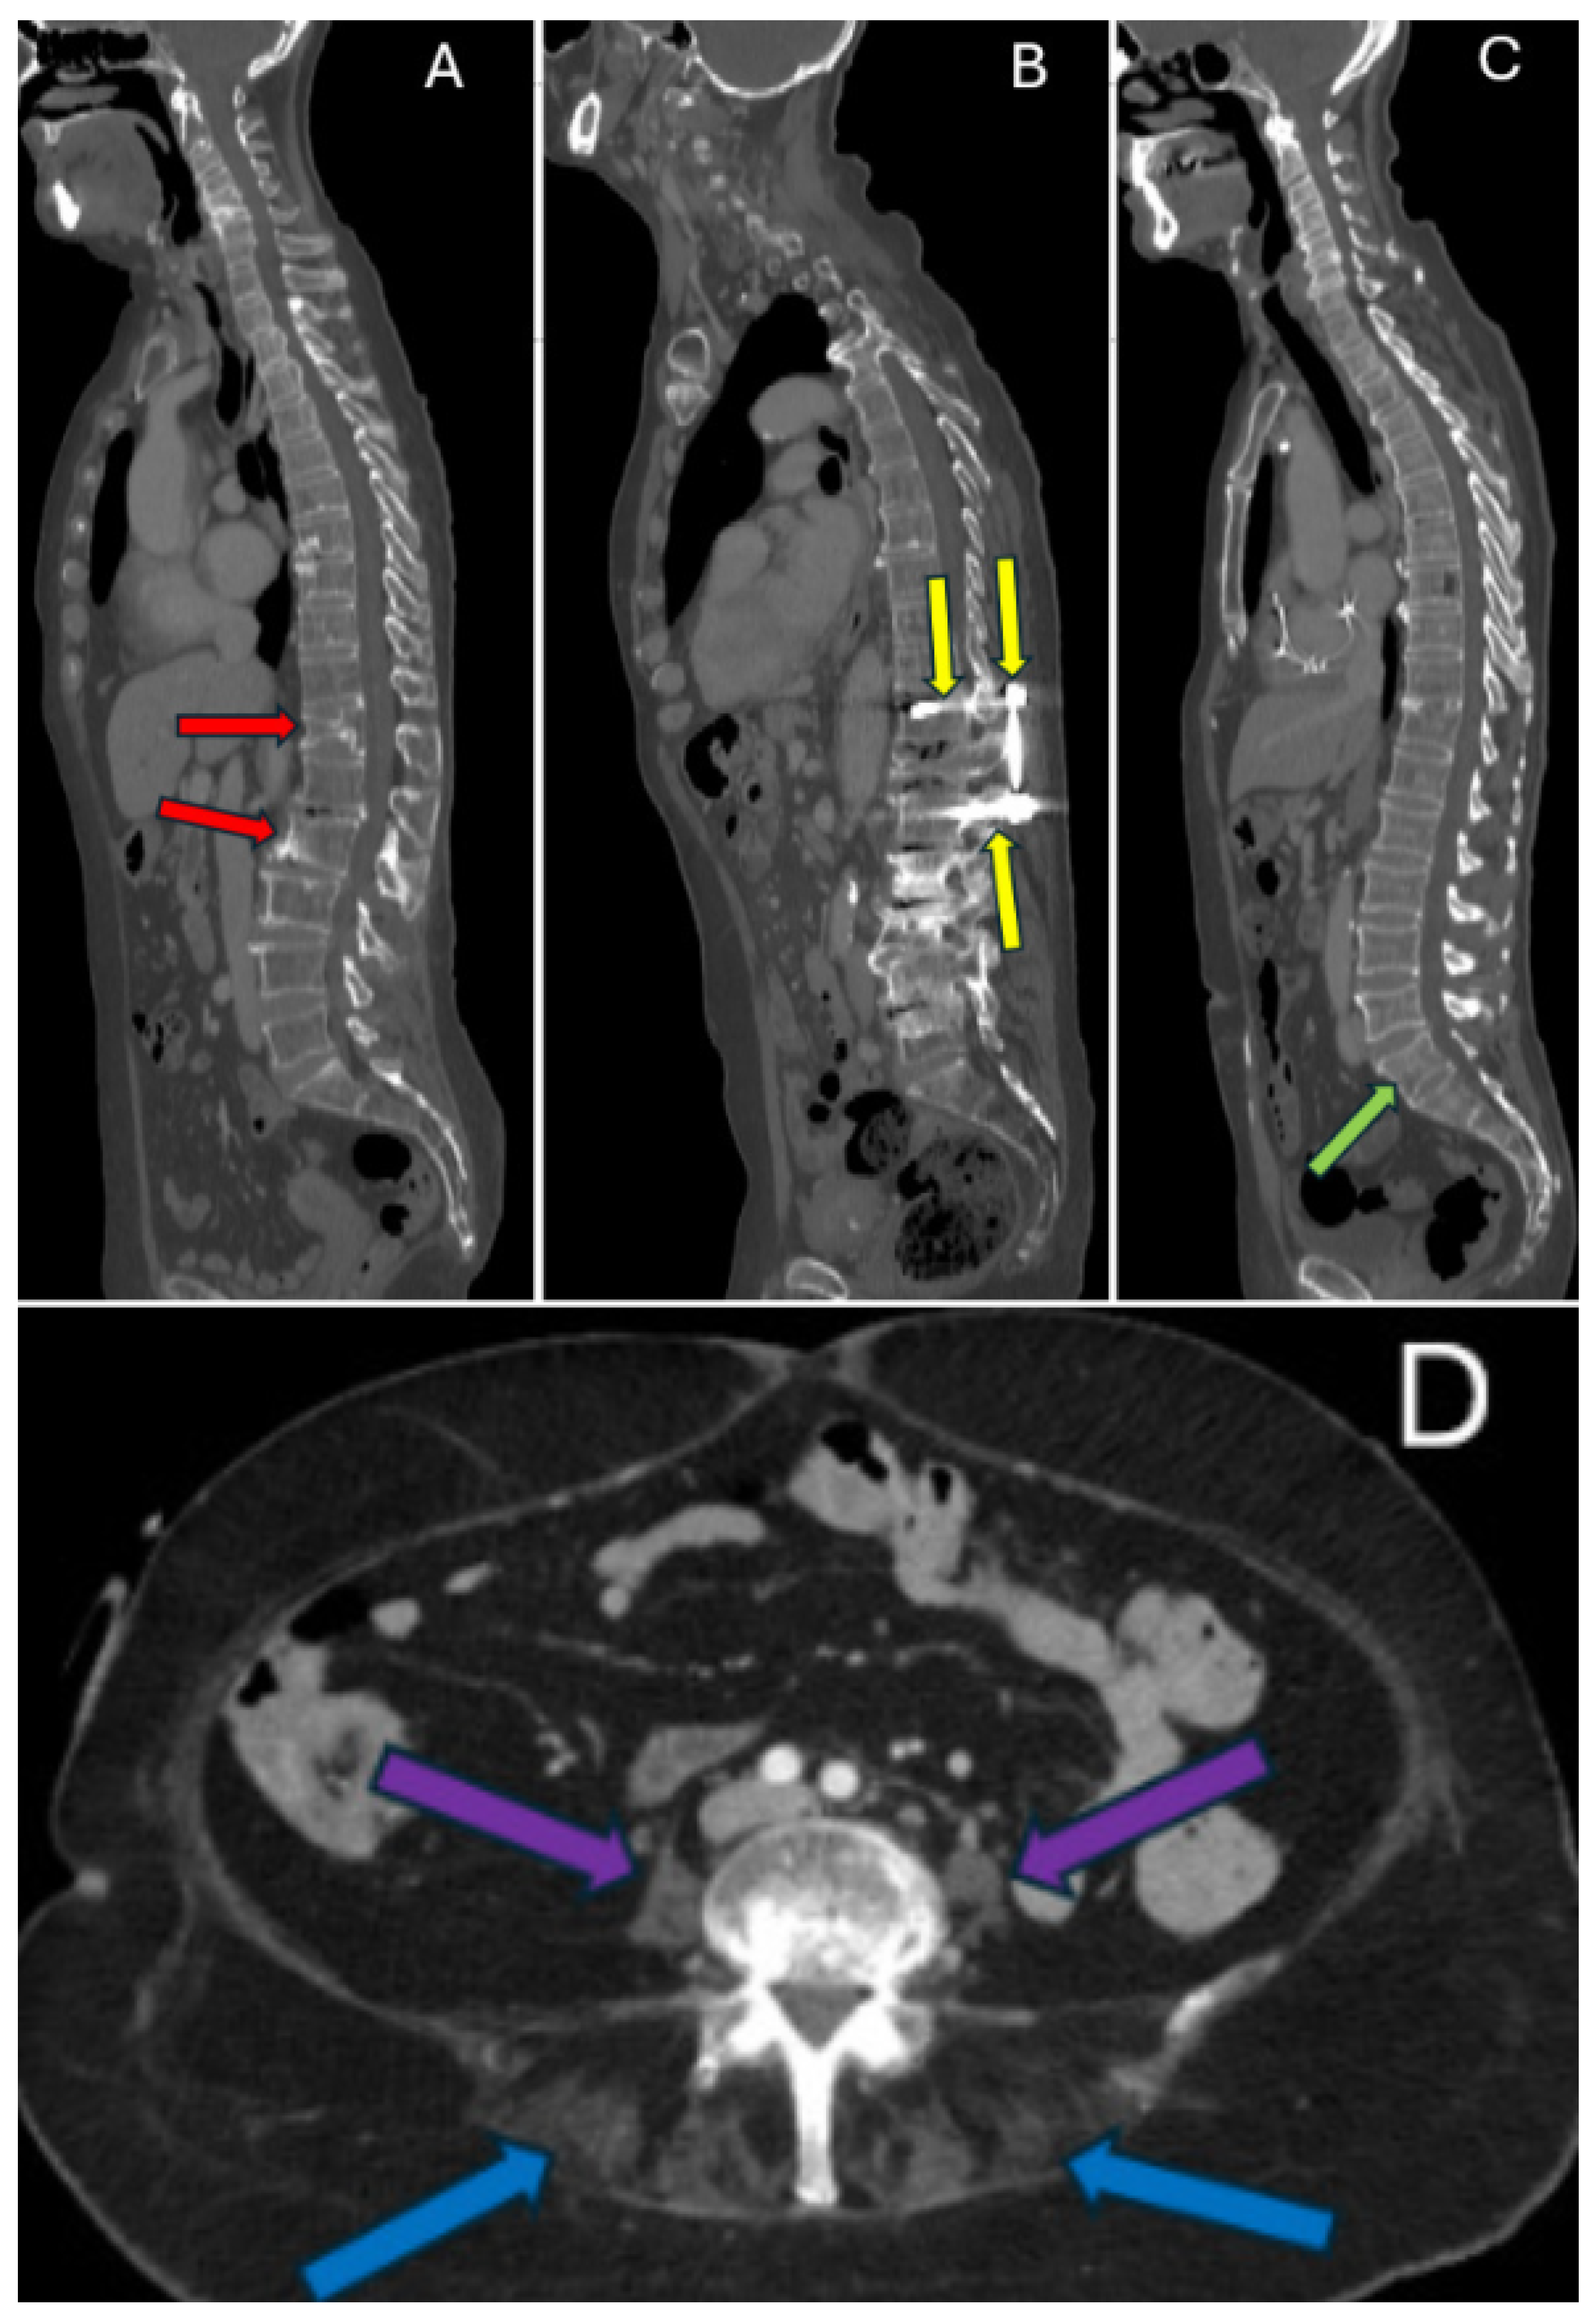
%), which was judged likely to reflect non-ambulatory status. Transitional vertebrae were evaluated separately in a sensitivity analysis rather than included in the main predefined exclusion set. Confounder assessment was performed by a board-certified radiologist with over 30 years of experience in musculoskeletal and spine imaging. Examples of these confounders are shown in
Figure 3. Excluded case identifiers and quality-control removals are listed in
Table A1.
2.3. Muscle Segmentation on CT
Nine bilateral trunk muscle groups (psoas, quadratus lumborum, paraspinal, latissimus dorsi, iliacus, rectus femoris, rhomboid, trapezius, and vastus) were manually segmented on 100 AtlasDataset CT scans using ITK-SNAP [
23,
24]. Manual reference labels were initially created by trained observers (Y.S., S.J., R.A., T.L., A.Y.P., A.J.V., and Z.Z.) and subsequently reviewed and refined by a board-certified radiologist (M.R.P.) with more than 30 years of experience.
The 100 manually segmented CT scans used for nnU-Net model development were divided 80:20 for model training and validation. These manual annotations served as ground truth for training a 3D nnU-Net [
18], which was then applied to segment the remaining AtlasDataset inference cohort (
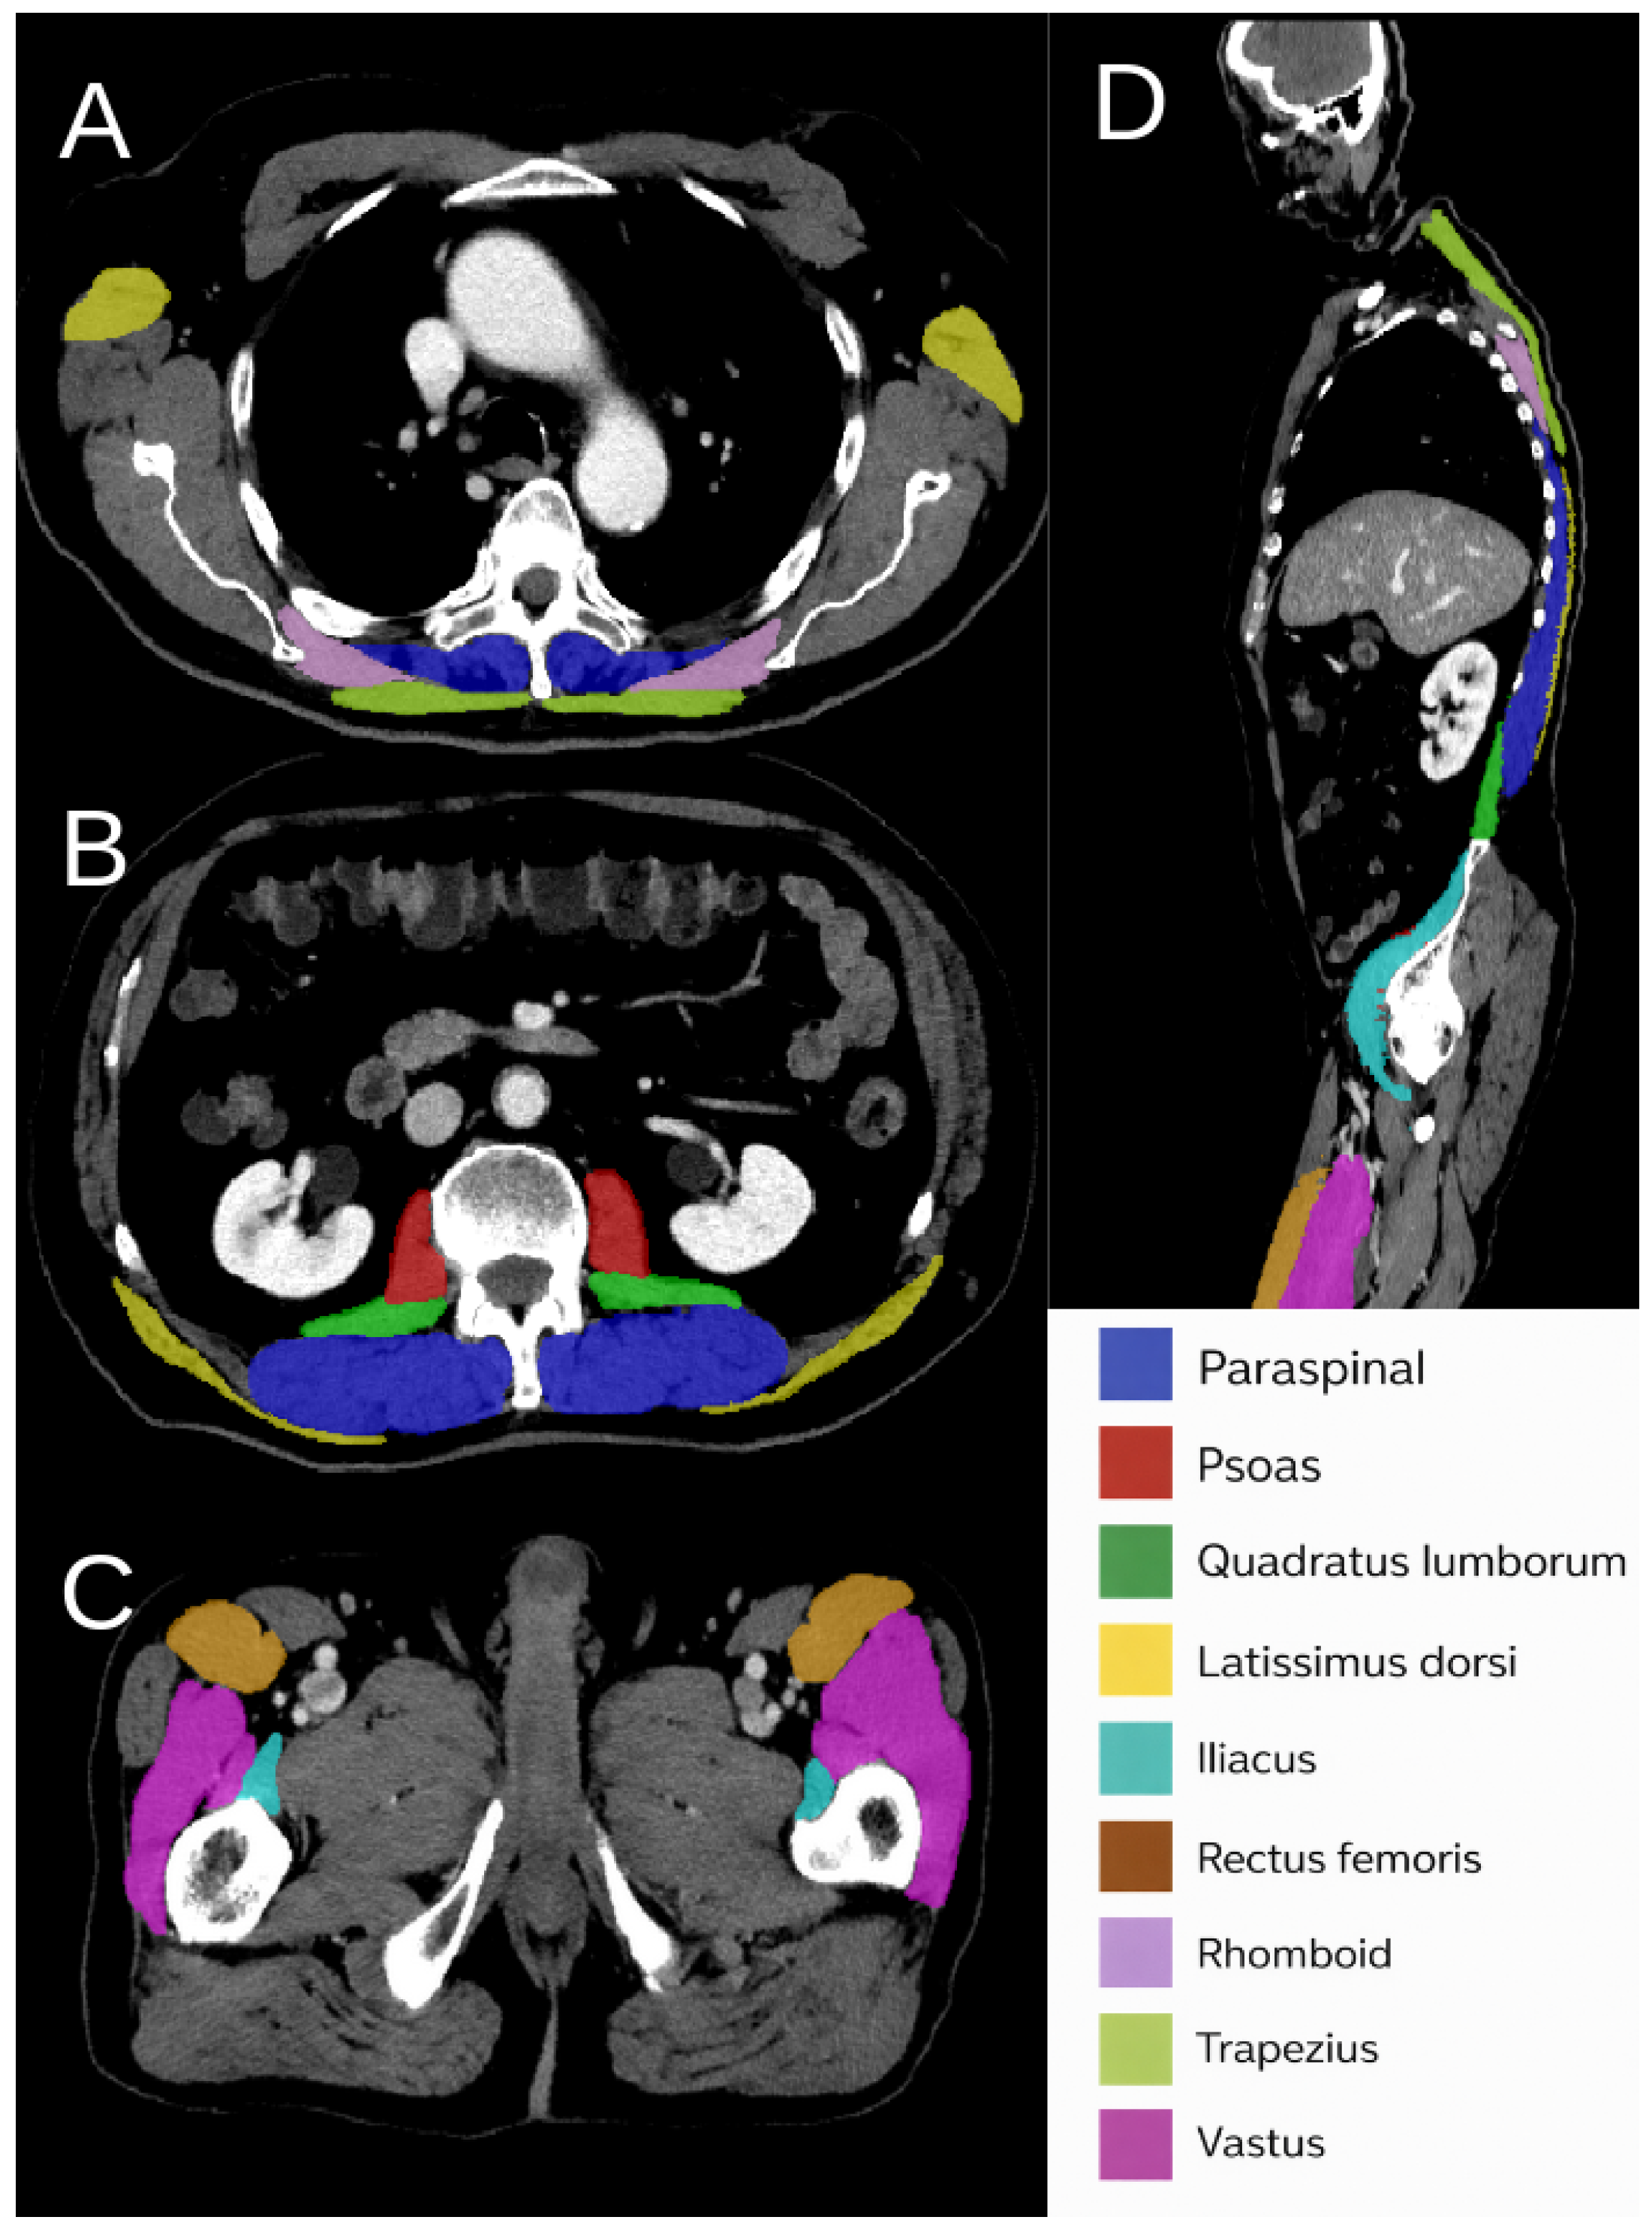
) for biomarker analyses, and the external TCIA cohort used for segmentation benchmarking. Representative manual annotations illustrating the muscle label taxonomy and craniocaudal distribution are shown in
Figure 4.
Figure 3.
Examples of confounders that may affect spine Cobb angle. (A): Vertebral body compression fractures at T12 and L2 (red arrows). (B): Spine surgery spanning from T11 to L3 with metallic rod and screws (Yellow arrows). (C): transitional vertebra with partial sacralization of L5 (green arrow). (D): Profound fatty atrophy of paraspinal muscles (blue arrows); psoas (purple arrows) is not compatible with ambulation.
Figure 3.
Examples of confounders that may affect spine Cobb angle. (A): Vertebral body compression fractures at T12 and L2 (red arrows). (B): Spine surgery spanning from T11 to L3 with metallic rod and screws (Yellow arrows). (C): transitional vertebra with partial sacralization of L5 (green arrow). (D): Profound fatty atrophy of paraspinal muscles (blue arrows); psoas (purple arrows) is not compatible with ambulation.
Preprocessing included isotropic resampling, intensity clipping to a soft-tissue Hounsfield unit range, and z-score normalization. A fixed training–validation split was used for model selection, with the external cohort reserved exclusively for final segmentation benchmarking. The detailed training configuration (loss functions, augmentations, learning schedule) and quantitative validation metrics are reported in
Section 2.6.
Figure 4.
Manual muscle annotations used for supervision and QA (CT). (
A–
C): representative axial slices at thoracic, abdominal, pelvic levels, respectively, with color-coded overlays for nine bilateral muscle groups (paraspinal, psoas, quadratus lumborum, latissimus dorsi, iliacus, rectus femoris, rhomboid, trapezius, vastus). (
D): mid-sagittal reconstruction showing the craniocaudal extent of the labels. Annotations were created in ITK-SNAP [
23] and used to train a single-fold nnU-Net
3d_fullresmodel [
18]; detailed training and validation results mentioned in
Section 2.6.
Figure 4.
Manual muscle annotations used for supervision and QA (CT). (
A–
C): representative axial slices at thoracic, abdominal, pelvic levels, respectively, with color-coded overlays for nine bilateral muscle groups (paraspinal, psoas, quadratus lumborum, latissimus dorsi, iliacus, rectus femoris, rhomboid, trapezius, vastus). (
D): mid-sagittal reconstruction showing the craniocaudal extent of the labels. Annotations were created in ITK-SNAP [
23] and used to train a single-fold nnU-Net
3d_fullresmodel [
18]; detailed training and validation results mentioned in
Section 2.6.
2.4. Muscle–Fat% Quantification on CT
Following automated or manual muscle segmentation, voxel-level intensity filtering was applied to quantify intramuscular fat content. Muscle masks were generated using the nnU-Net model [
18], and voxel Hounsfield units (HU) were extracted within each segmented muscle. Voxels with HU values below
were classified as fat-containing tissue, based on established CT attenuation thresholds for intramuscular adiposity and muscle quality assessment [
2,
9,
10]. Intramuscular fat fraction (muscle–fat%) was then computed as the ratio of low-attenuation voxels (HU
) to the total number of voxels within each 3D muscle mask.
For the quality-control comparison on development scans, intramuscular fat fraction (muscle–fat%) was computed twice per muscle per subject—once using the manual mask and once using the automated mask from the frozen model—yielding paired measurements for mean ± SD summaries and tables reported in
Section 3.
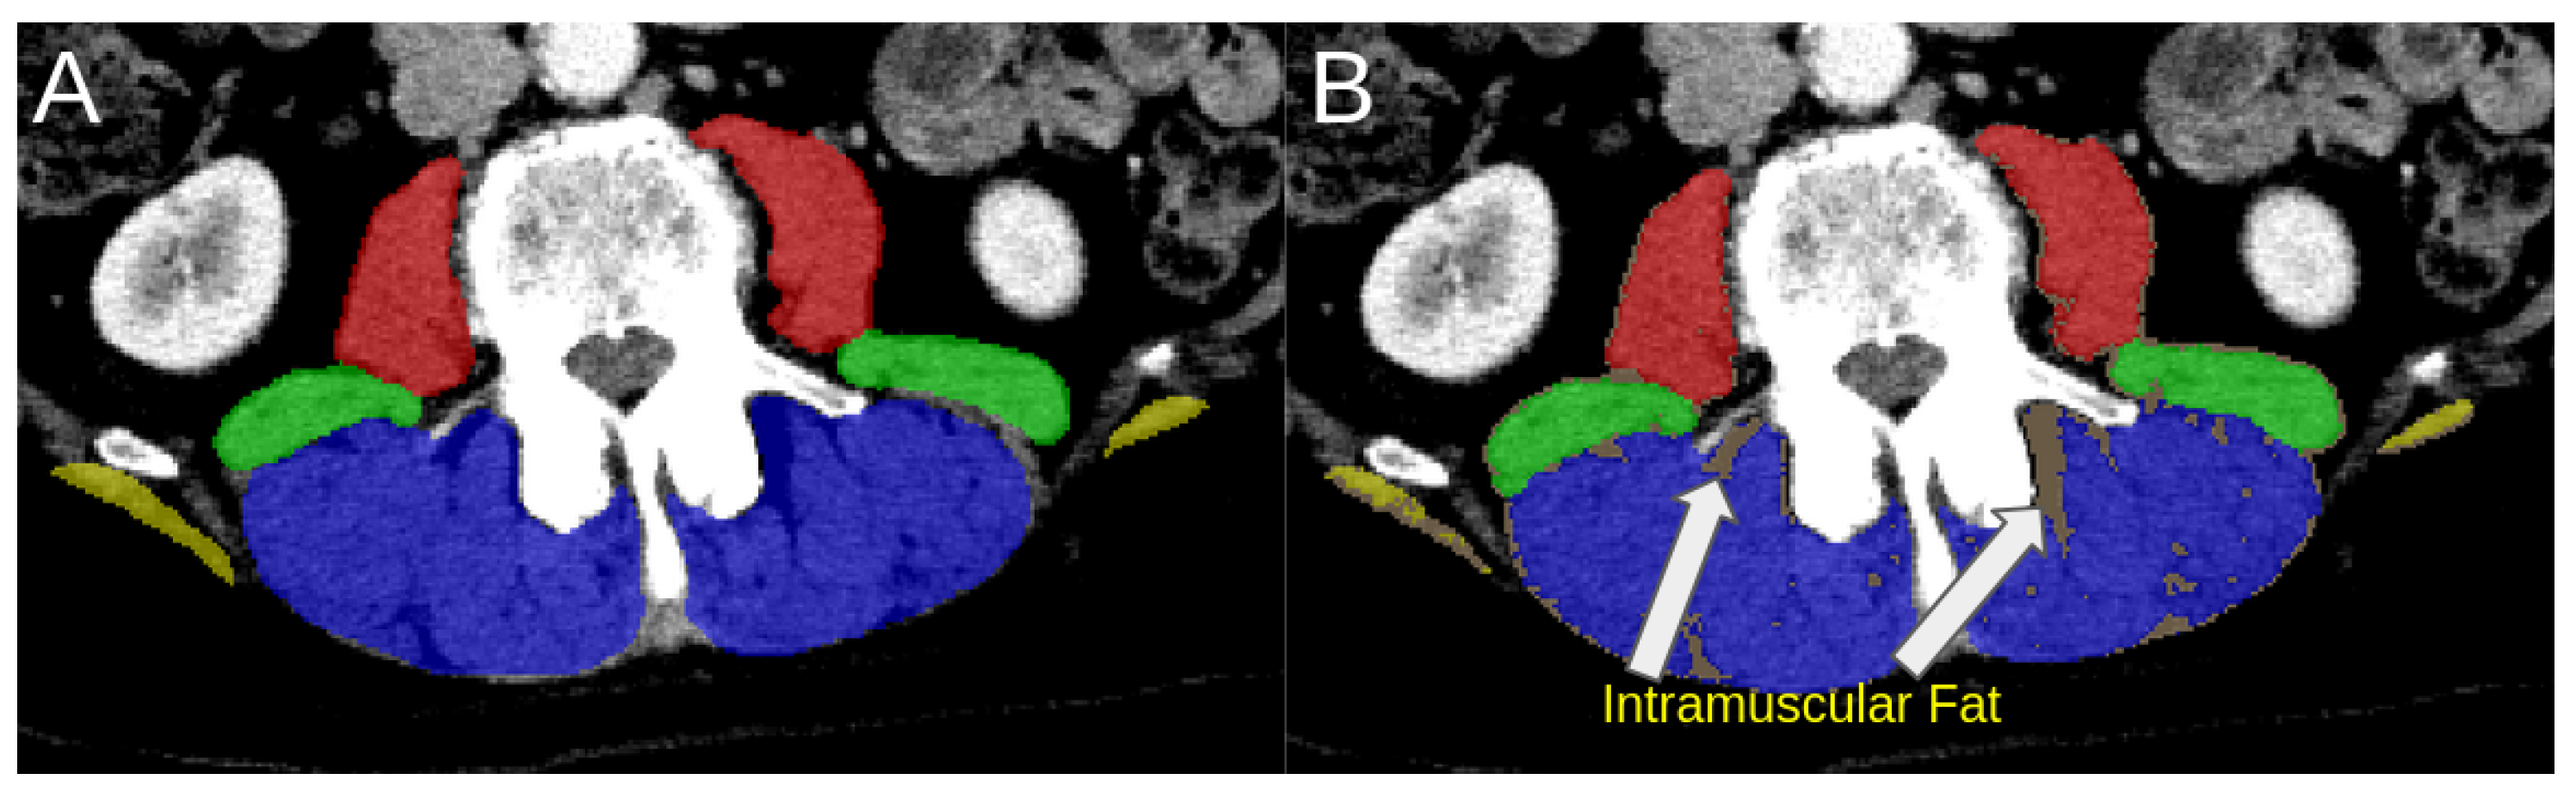
Figure 5 illustrates the voxel-based filtering process and its effect on differentiating healthy muscle from fatty atrophy.
2.5. Statistical Analysis
The primary endpoint was the association between thoracic supine kyphosis, quantified by the Cobb angle on the sagittal plane, and muscle–fat% derived from CT. All analyses were conducted in Python 3.10.12 using
scipy.statsand
pingouin [
25], with visualizations generated in
matplotlib.
Thoracic supine kyphosis measurements for all internal cases were performed independently by four trained observers. Inter-observer consistency was quantified using the two-way random-effects intraclass correlation coefficient ICC(2,
k) with absolute agreement and bootstrap 95% confidence intervals [
21]. The mean Cobb angle across observers was used in all subsequent analyses. Detailed four-observer reliability summaries are reported in
Table A2.
For segmentation model development, nnU-Net training and validation were performed using fixed AtlasDataset partitions ( for training and for validation). These cohorts were used exclusively for model optimization and were not used for segmentation benchmarking.
For biomarker analysis, Pearson’s correlation coefficient (r) was used to assess the relationship between thoracic supine Cobb angle and muscle–fat%, with two-sided p-values reported. Correlations were computed in AtlasDataset in two cohorts: (i) the manual cohort (), and (ii) the automated cohort (). Baseline correlations were computed on the full cohorts. Because correlations were evaluated across nine muscle groups, p-values are interpreted cautiously as exploratory.
Sex-stratified correlations are reported in
Table A3. Additional sensitivity analyses for vertebral compression fractures and transitional vertebrae are reported in
Table A4 and
Table A5.
The external cohort was used exclusively for segmentation performance verification and was not included in any muscle–fat% or supine kyphosis correlation analyses due to inadequate dataset information.
2.6. Model and Training
A 3D nnU-Net
3d_fullres configuration [
18] was trained for automated trunk muscle segmentation using a compound Dice+cross-entropy loss function. The total loss
combined the soft Dice loss
and voxel-wise cross-entropy loss
as:
where the Dice term was defined as:
with
and
denoting the predicted and ground-truth probabilities for class
c, respectively, and
a small constant for numerical stability. The cross-entropy term penalized voxel-wise misclassification:
The model was optimized using the AdamW optimizer with a cosine annealing learning rate schedule (initial , minimum ). A batch size of 2 and gradient accumulation of 4 steps were employed to fit the 3D context window (patch size ) within GPU memory constraints. Weight decay () and exponential moving average (EMA) parameter tracking () were used to stabilize training.
Standard nnU-Net data augmentations, including random rotations, elastic deformations, gamma correction, mirroring, and intensity jitter, were applied on-the-fly. We used nnU-Net’s CT preprocessing, with volumes resampled to 2.5 × 0.871 × 0.871 mm (z,y,x) using cubic interpolation in-plane and nearest along z for images. Intensities were clipped to −95 to +116 HU based on dataset foreground percentiles (0.5th–99.5th), and then z-score-normalized per case. Specific preprocessing information can be found at the publicly available code repository.
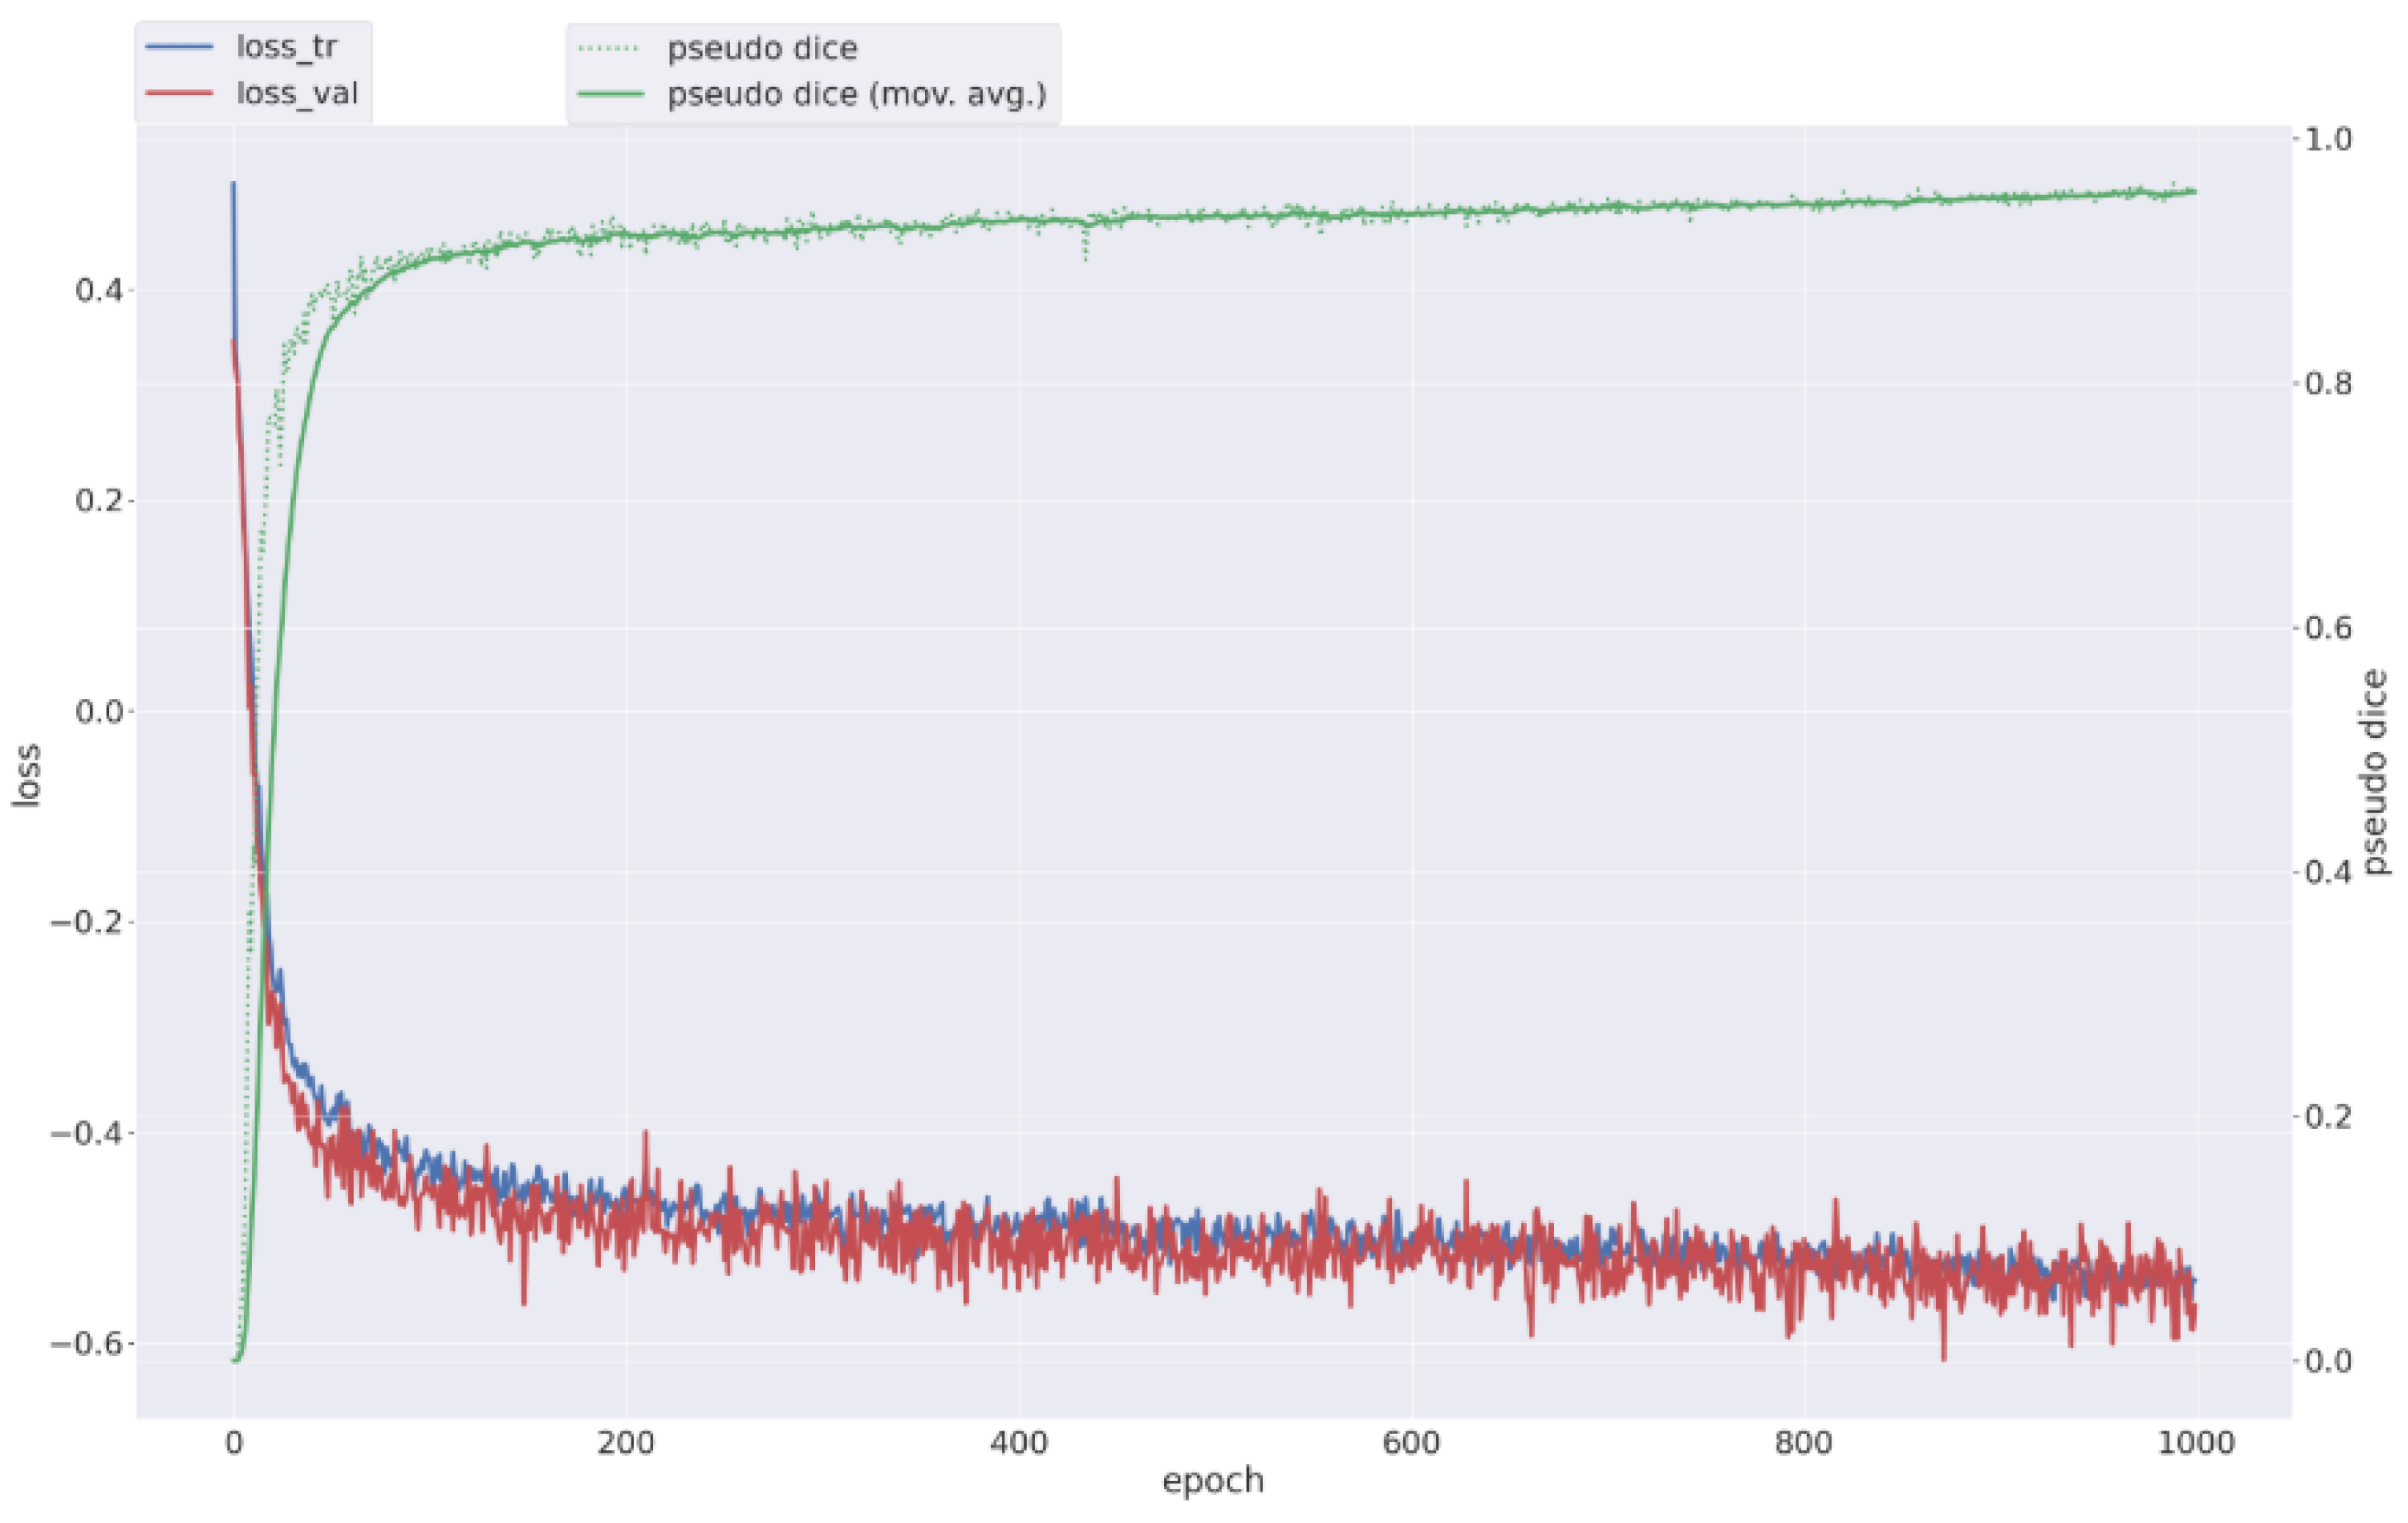
Model convergence was monitored through pseudo-Dice and EMA validation metrics across epochs. Training and validation trajectories are shown in
Figure 6, demonstrating stable optimization and consistent convergence behavior.
2.7. Computational Environment
Model training and inference were conducted on a Linux (x86_64) workstation equipped with an NVIDIA GeForce RTX 4090 GPU (24 GB GDDR6X memory). Key software dependencies and hardware specifications are summarized in
Table 1 to ensure reproducibility.
4. Discussion
4.1. Interpreting the Link Between Muscle–Fat% and Thoracic Curvature
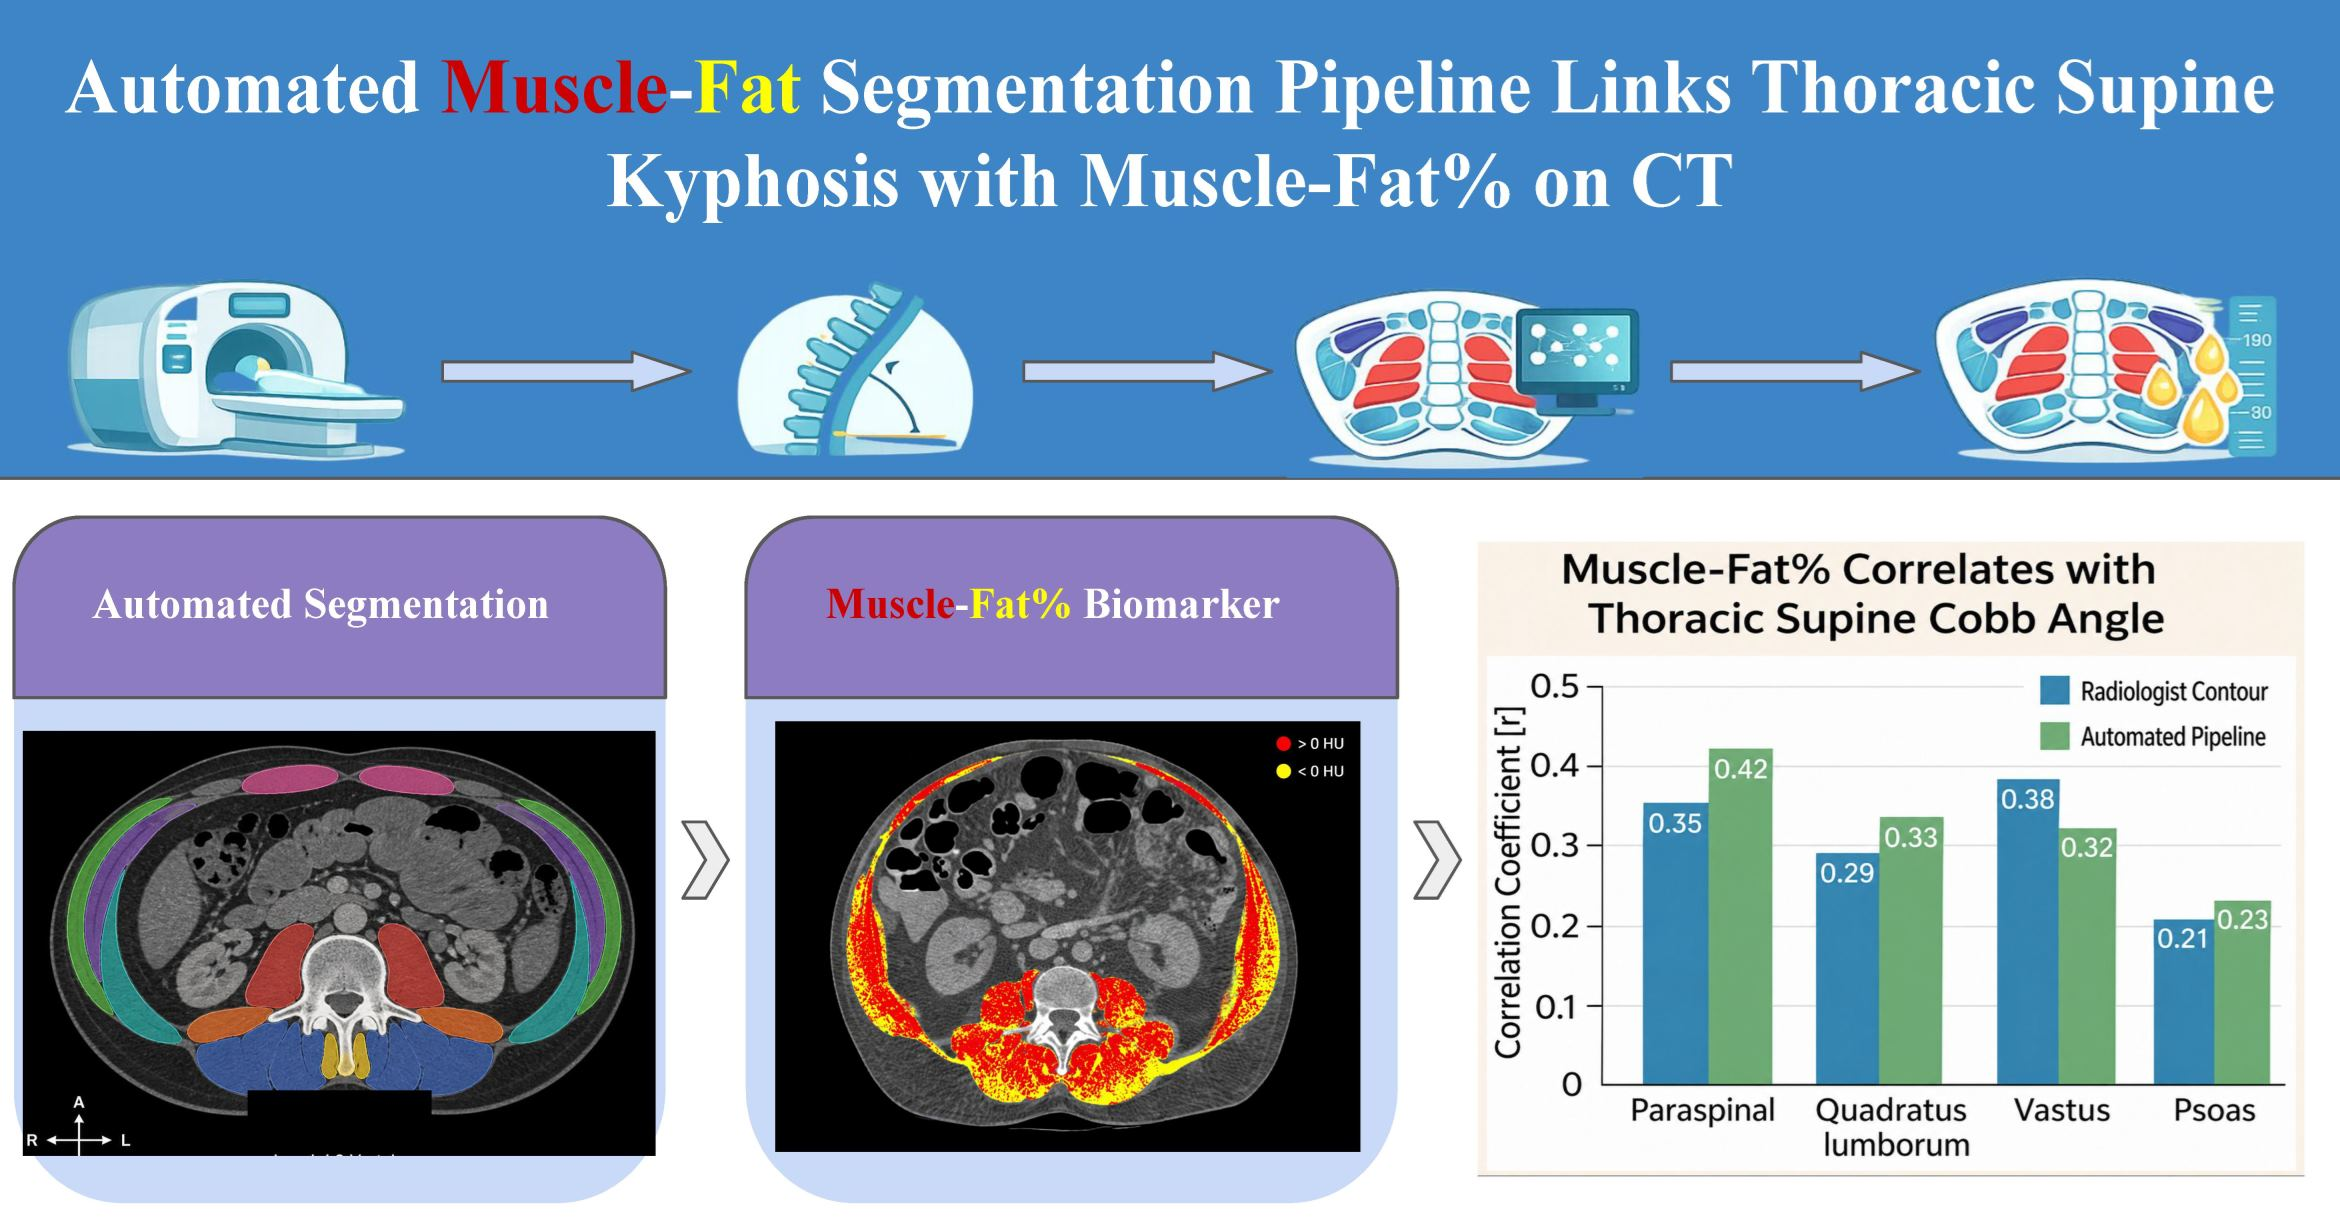
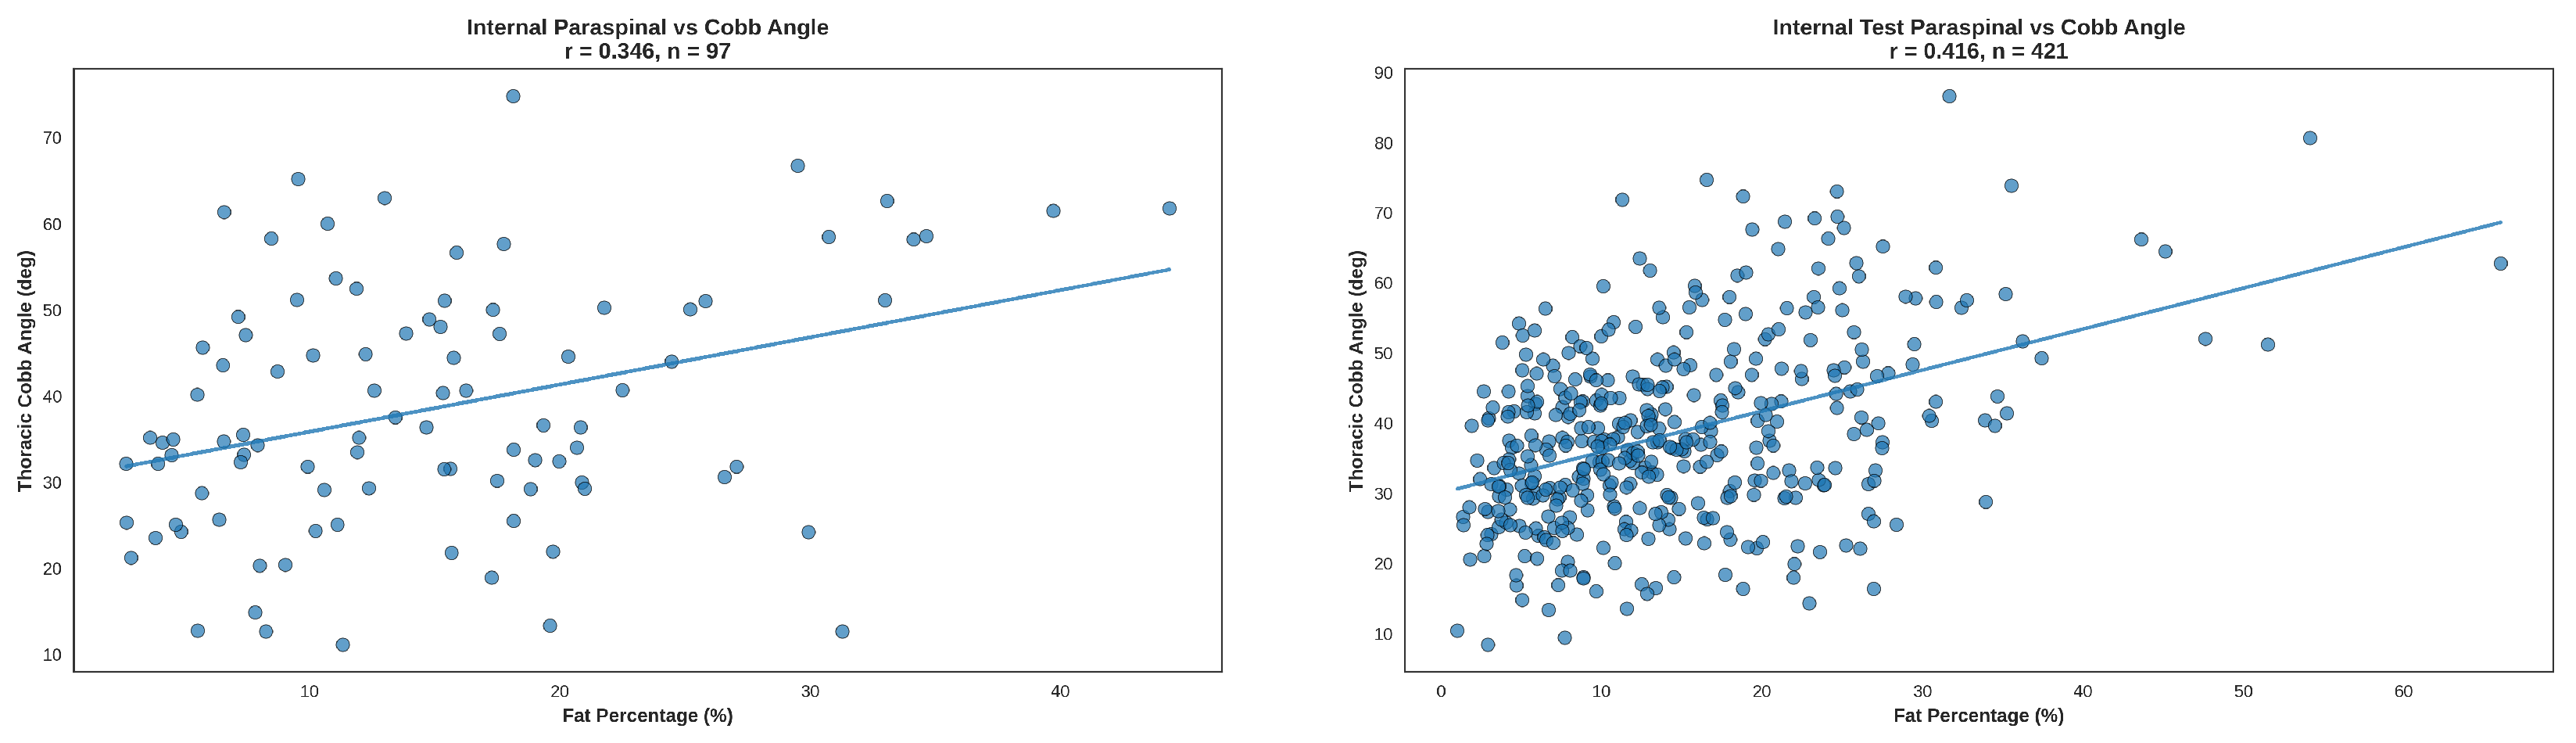
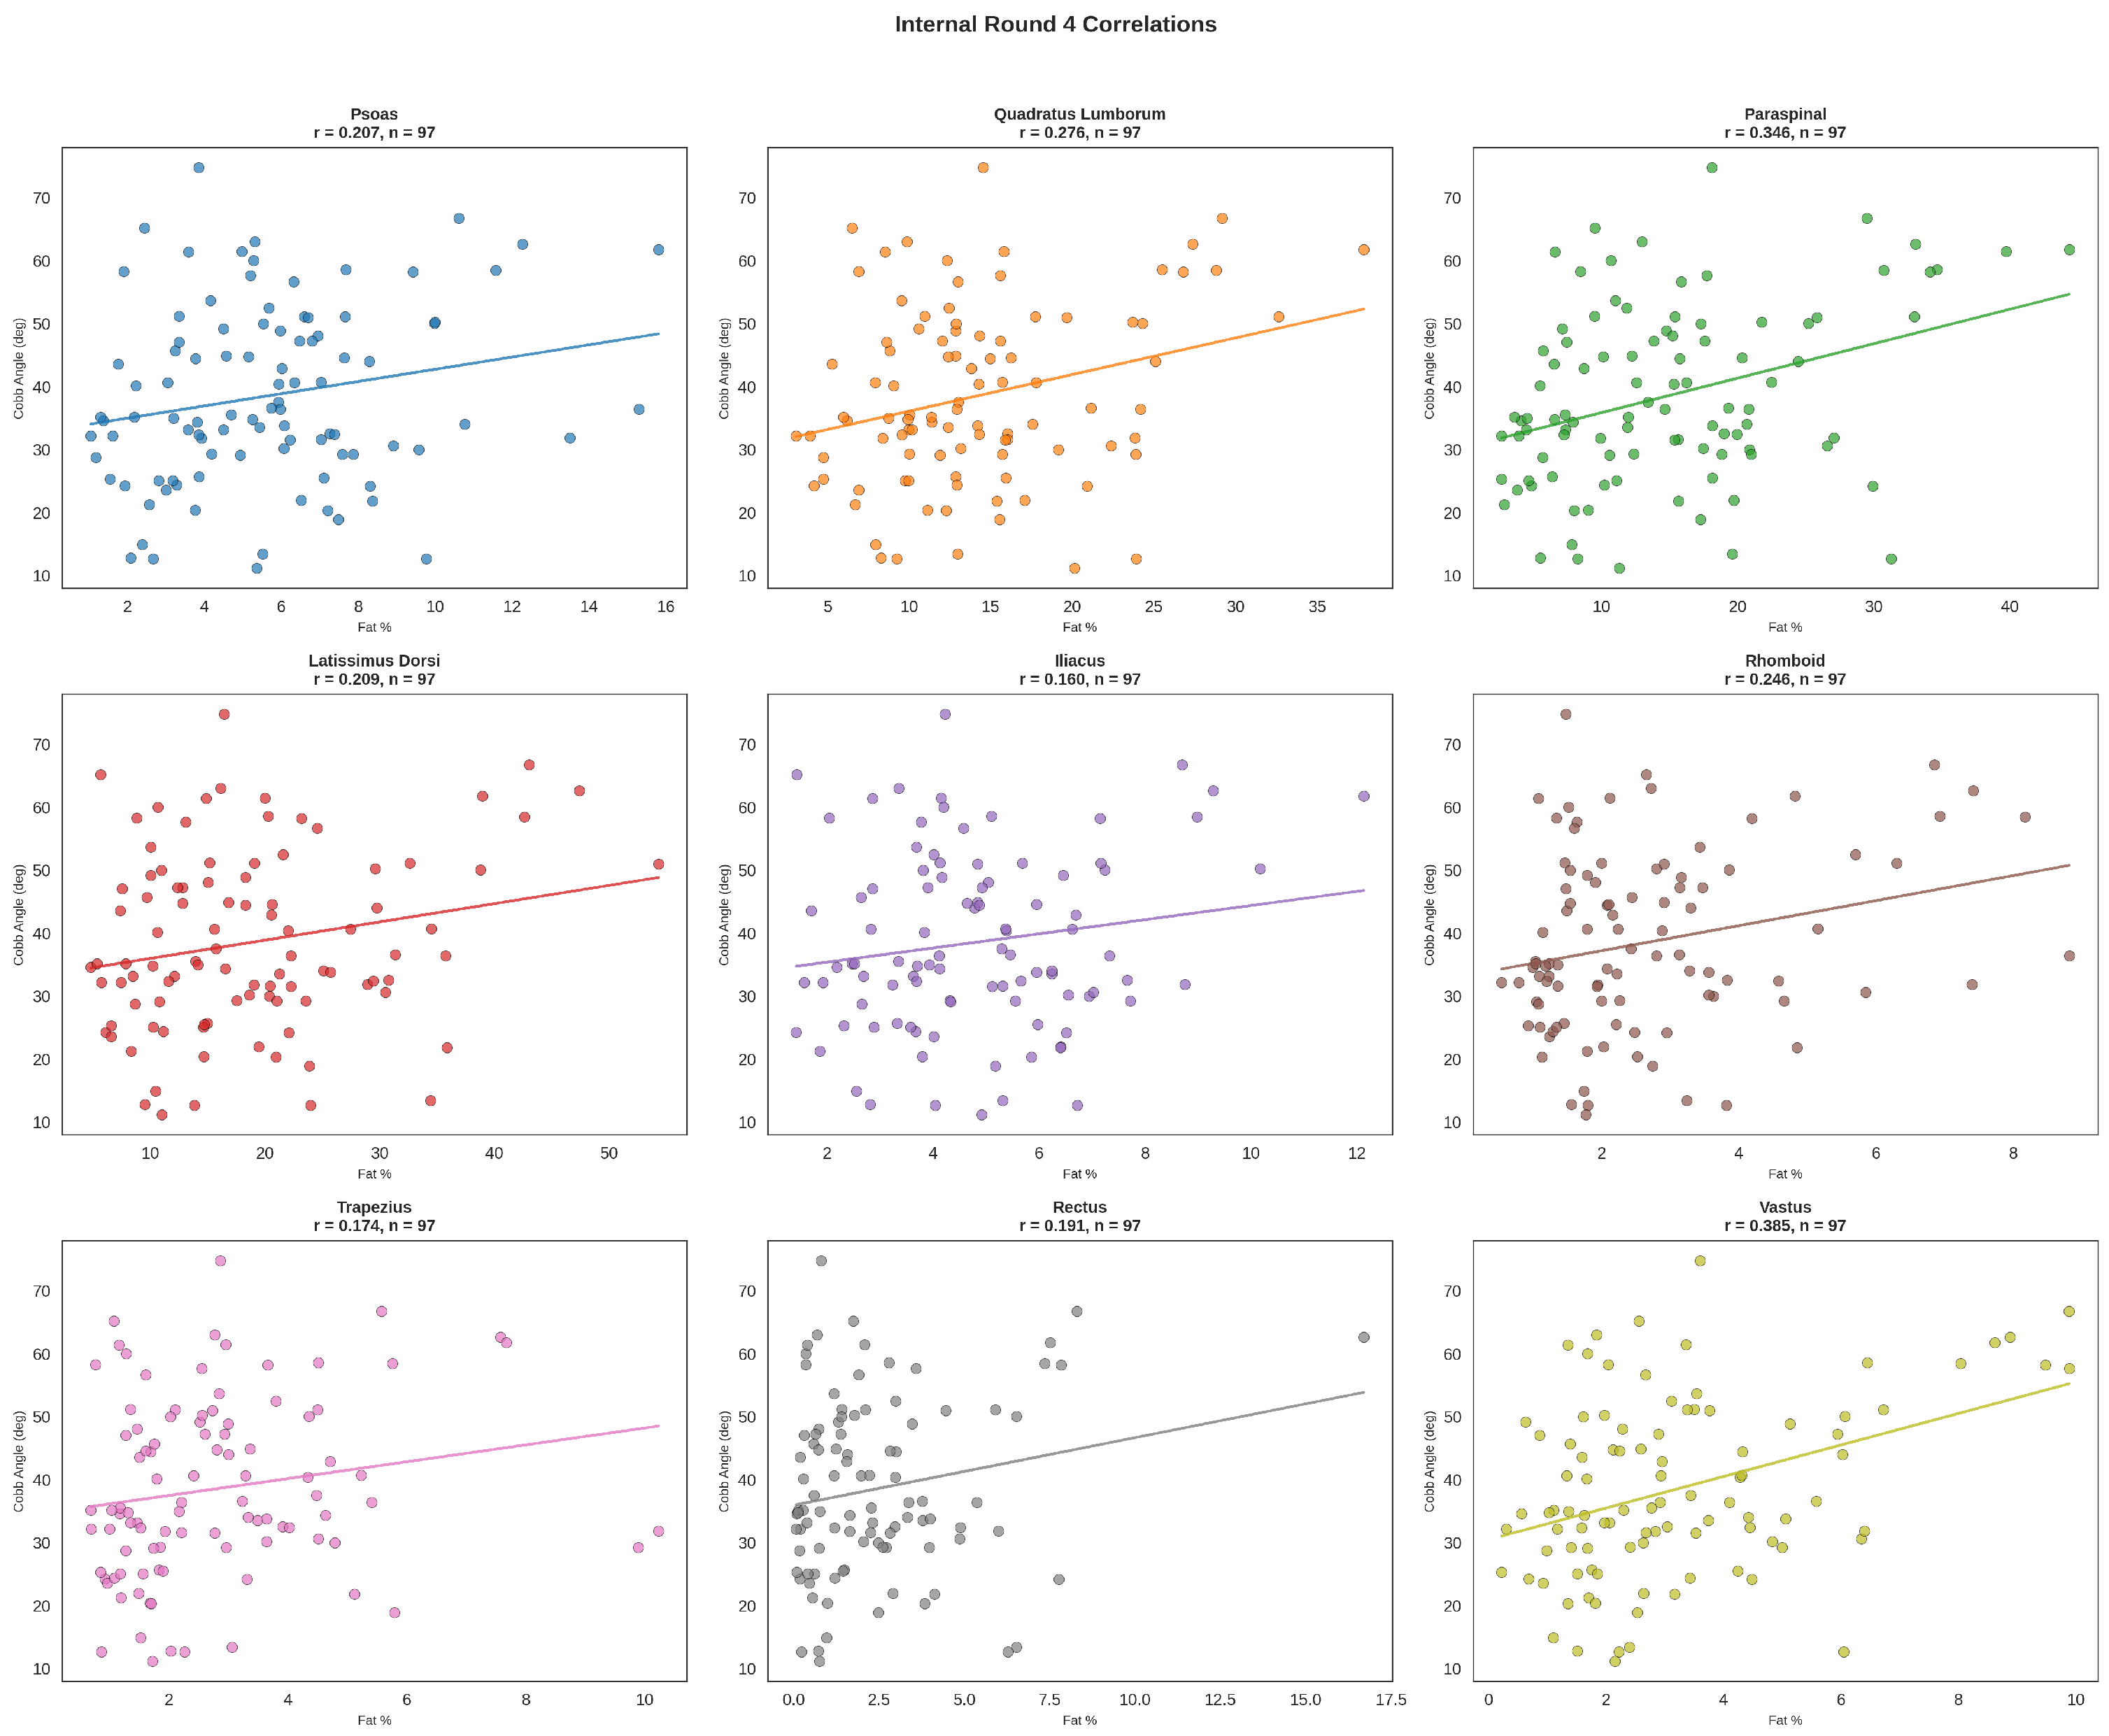
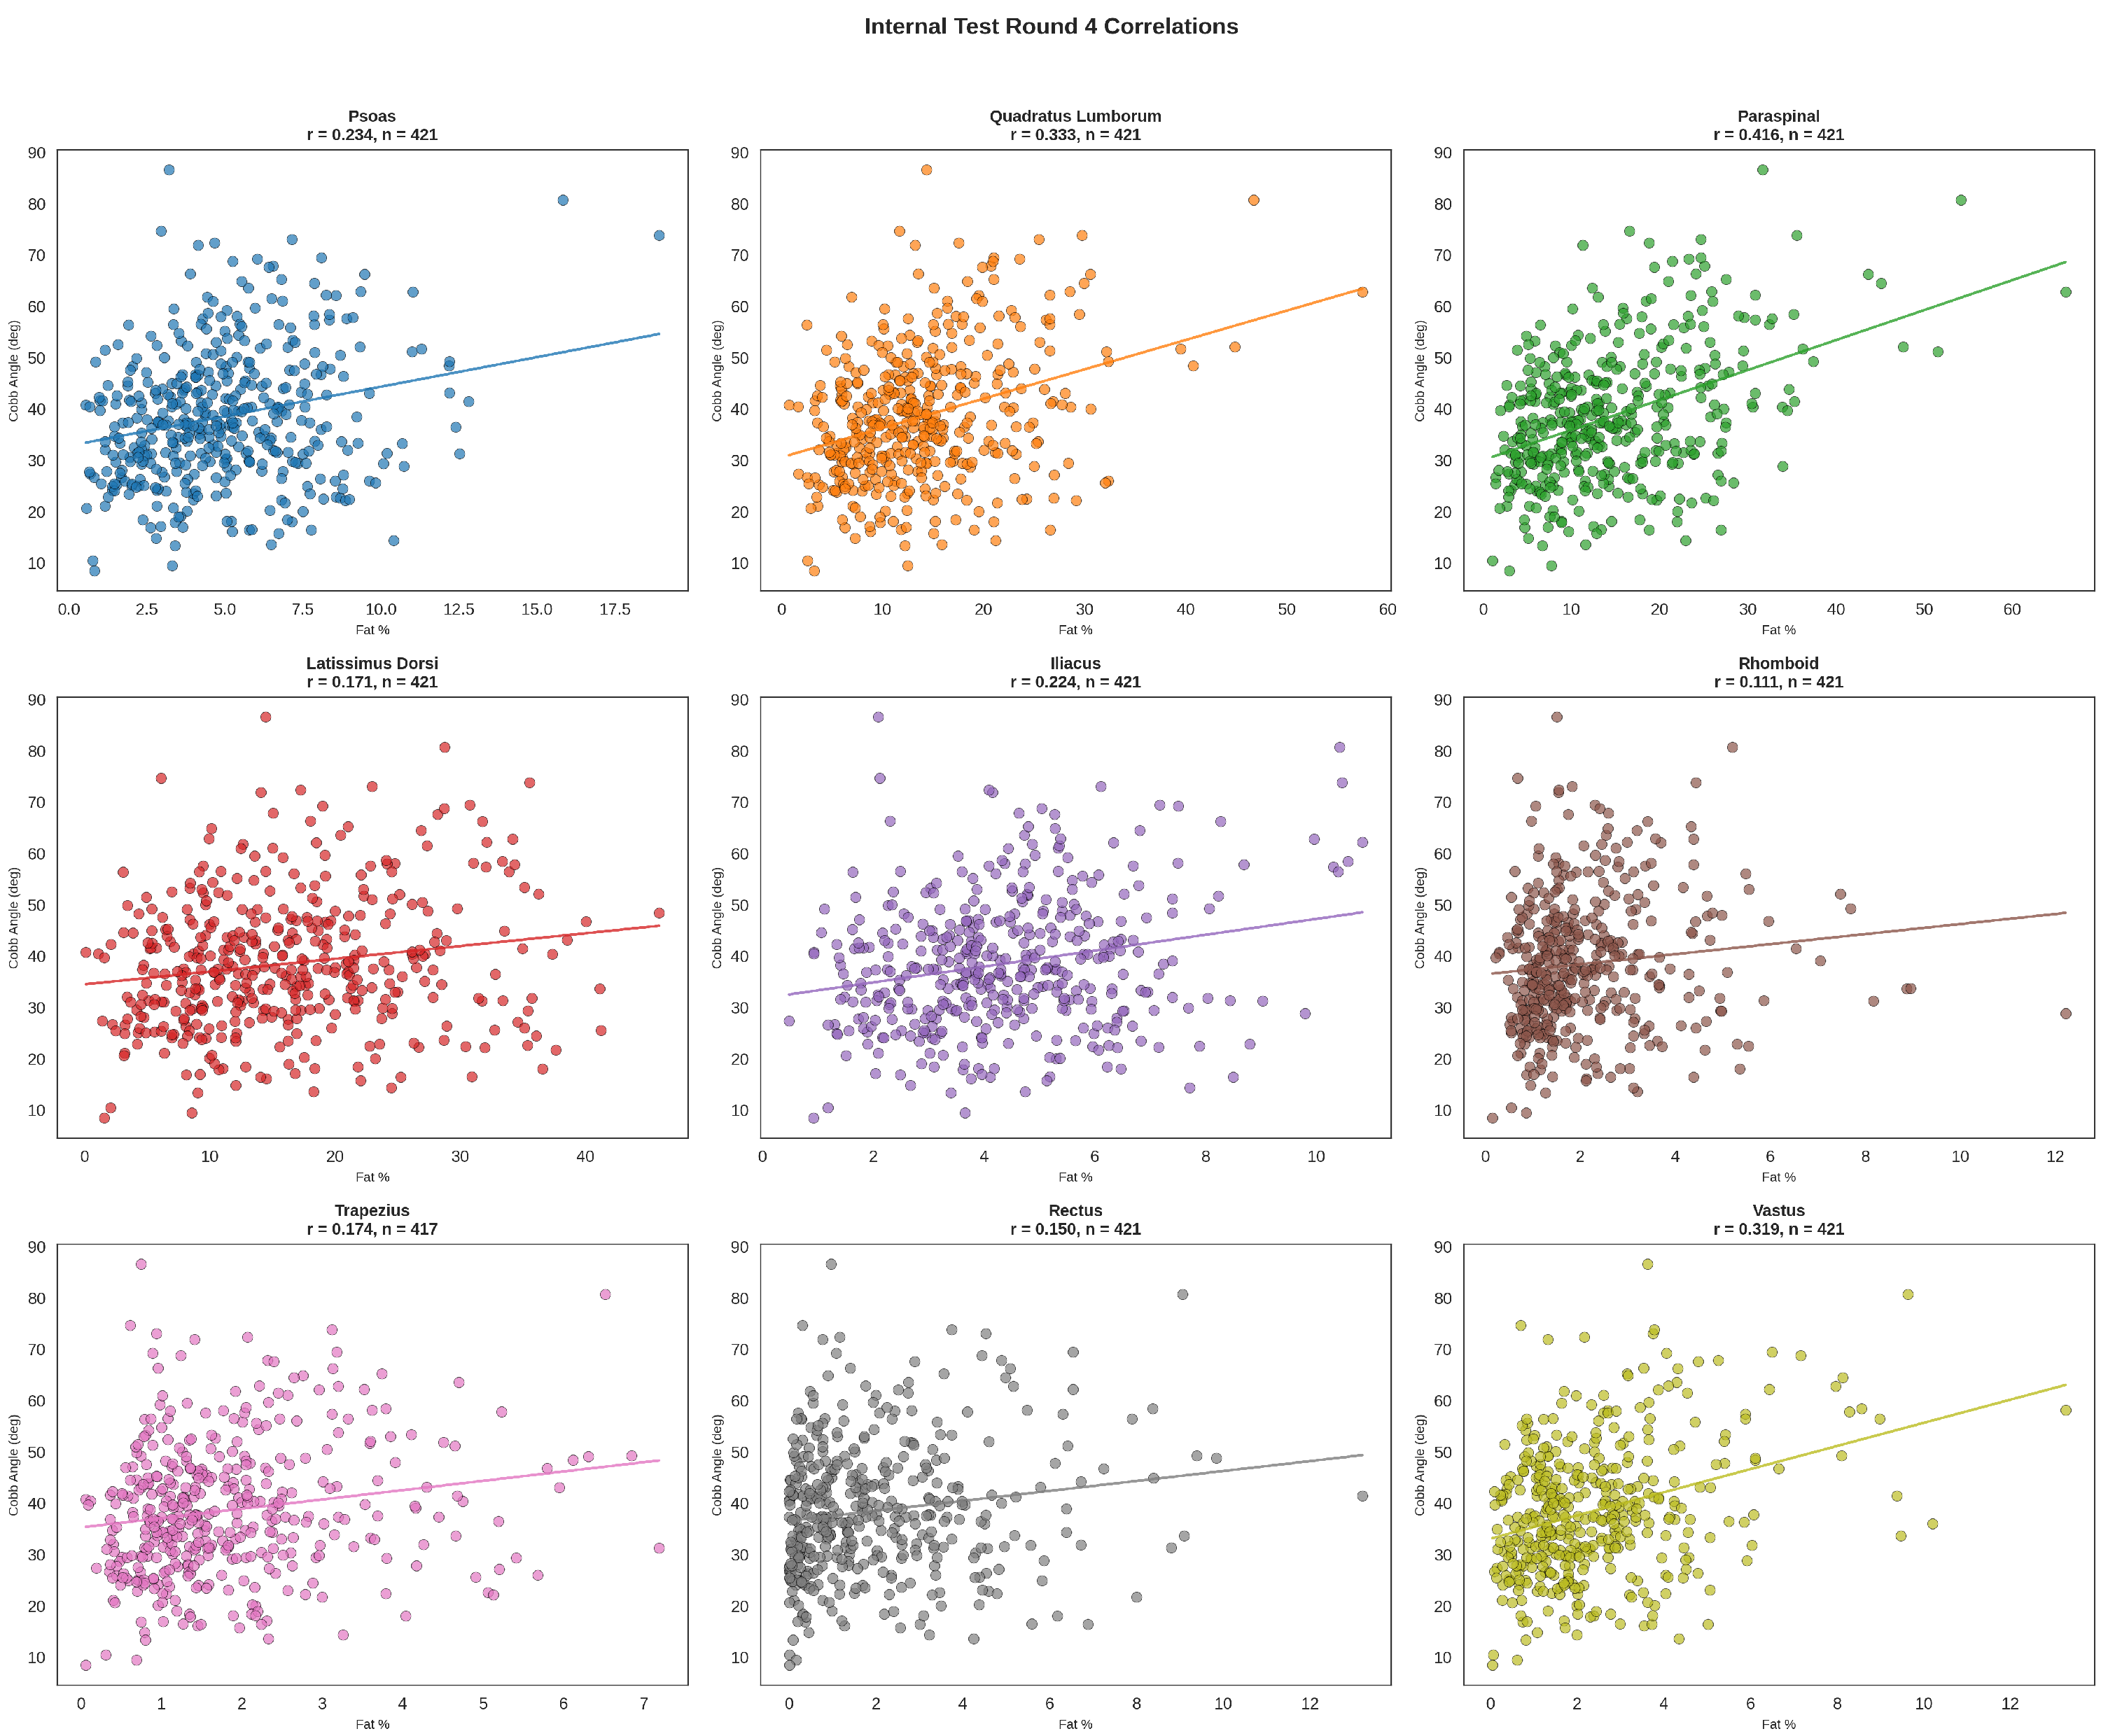
Across both the manual and automated cohorts, higher thoracic supine kyphosis was consistently associated with greater intramuscular fat percentage, confirming a relationship between muscle fatty atrophy and increased thoracic supine kyphosis (
Table 4;
Figure 8;
Figure A2 and
Figure A3). This association was similar in males and females and did not appear to be materially affected by vertebral compression fractures or transitional vertebrae. Because this open-source dataset includes only images and no metadata, the effects of demographic variables not apparent on imaging could not be assessed; the potential influence of additional covariates (e.g., age, body mass index, physical activity level, or comorbidities) could not be evaluated.
The strongest relationship was found in the posterior thoracolumbar paraspinal extensor muscles, with weaker relationships in other muscles. This pattern mirrors the biomechanical hierarchy of postural control, with the paraspinal muscles, which are most responsible for counteracting anterior flexion, demonstrating the highest degree of fatty infiltration with increasing supine kyphosis. This convergence across datasets reinforces the biological plausibility of muscle–fat% as a muscle quality biomarker and aligns with prior literature linking paraspinal degeneration to sagittal imbalance and deformity progression [
12,
13,
14,
15,
16,
17] (see also
Table 4). Our findings are also broadly consistent with systematic review evidence that paraspinal fatty infiltration is a recurrent feature across spine-related imaging studies, while extending that literature to automated CT-derived multi-muscle quantification in supine thoracic curvature assessment [
27]. The fact that even thigh muscle–fat% in the vastus significantly correlated with thoracic supine kyphosis suggests that generalized fatty muscle atrophy is associated with increasing supine kyphosis [
8,
11].
The higher mean fat percentage observed in the paraspinal (15%) and quadratus lumborum (14%) muscles across all cases may reflect the fact that these muscles occupy anatomically constrained compartments defined in part by surrounding osseous structures, such that loss of contractile muscle tissue is preferentially replaced by fat. By contrast, muscles with greater freedom to decrease in size may show lower measured muscle–fat%, because loss of contractile tissue does not necessarily require volumetric replacement by fat. This may partly explain the lower mean values observed in the vastus (3.2%), rectus femoris (2.5%), trapezius, and rhomboid. Trapezius also had a high mean muscle–fat% which may reflect its complex, sheet-like anatomy, thin with a lot of surface which accentuates partial volume averaging incorporating surface fat into the segmentations. So it is not surprising that paraspinal and quadratus both had strong correlations. Strong vastus (a leg muscle not even touching the spine) muscle–fat% correlation with supine kyphosis suggests that generalized muscle atrophy throughout the body correlates with thoracic supine kyphosis.
4.2. Impact of Confounder Control and Sex Stratification
We evaluated whether predefined confounders materially influenced the observed associations between thoracic supine kyphosis and muscle–fat% by recomputing correlations before and after exclusion of prior spine surgery and profound fatty atrophy (paraspinal muscle–fat%
%). Across both internal cohorts, excluding these cases yielded consistently higher correlation coefficients across all nine muscles (
Table 4). This pattern supports the validity of the exclusion criteria: postoperative anatomy and extreme, likely non-ambulatory fatty degeneration plausibly disrupt the biomechanical relationship between trunk muscle quality and upright sagittal alignment, and their removal strengthens the underlying signal.
In contrast, stratification by sex showed only modest differences in effect size across muscles (
Table A3). While some muscle groups demonstrated numerically higher or lower correlations in one sex, the overall pattern of association remained similar and did not indicate a systematic sex-driven confounding effect. These results suggest that sex is unlikely to be a dominant confounder for the supine kyphosis–muscle–fat% relationship in this dataset, although larger cohorts with complete demographic metadata would enable more definitive covariate-adjusted modeling. Sex-stratified correlations were directionally consistent and did not materially change interpretation; full sex-split results are reported in
Table A3. Although transitional vertebrae at L5-S1 could confuse observers about the vertebral body levels, removing these cases with transitional vertebrae did not affect the results.
4.3. Cobb Angle Measurements
Cobb angle is prone to bias and is known to have limited reproducibility for single observers [
3,
4,
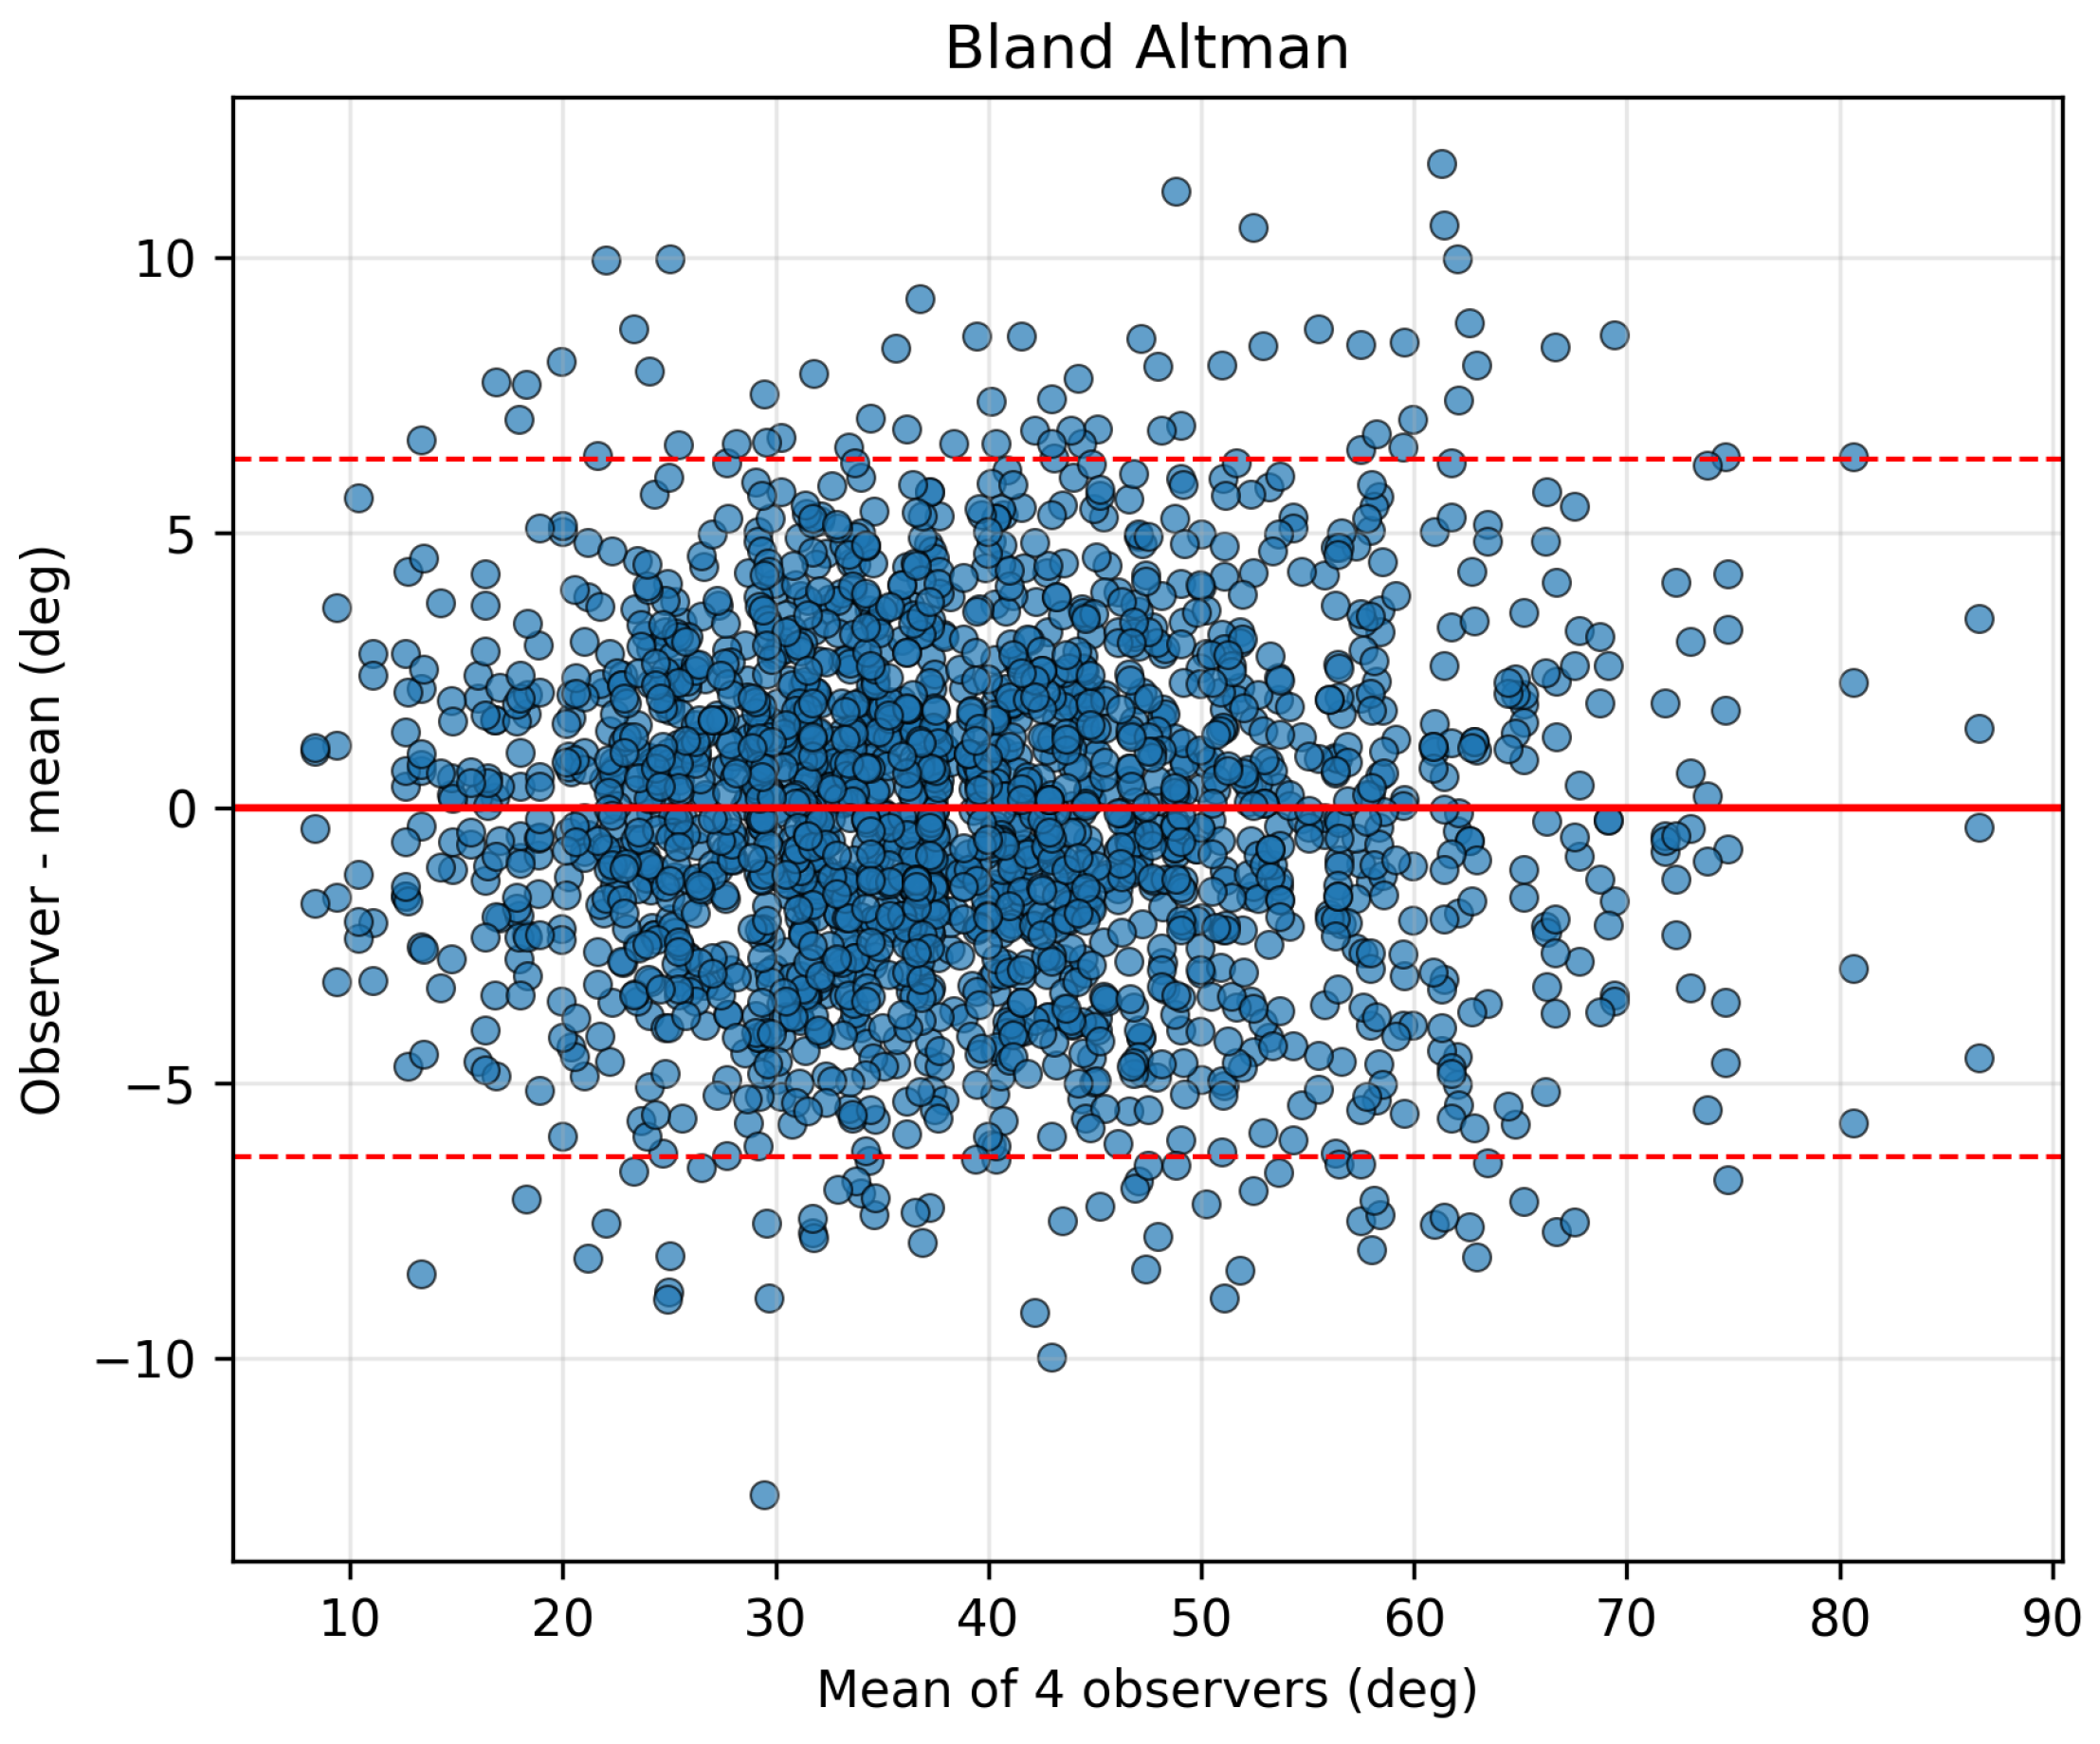
5]. The mean across-rater per-case standard deviation of thoracic supine Cobb angle across the four observers was 3.4°, indicating that a typical single observer’s measurement differs from the four-observer mean by a few degrees. The Bland–Altman plot (
Figure 7) [
26] shows that 5% of cases are more than 6 degrees different from the mean of all observers. This supports the use of muscle–fat percent as a complementary and automatic method for evaluating hyperkyphosis risk on CT scans. Muscle–fat% also identifies targets for intervention to stimulate muscle strength and can precisely track progress in rebuilding muscle strength. Analogous muscle composition biomarkers may also be measurable on MRI, which could extend this framework to non-ionizing imaging modalities.
4.4. Pipeline Significance: Toward Automated Surrogate Biomarkers
The integration of reliable manual references, deep learning segmentation, and standardized HU-based fat quantification forms a reproducible end-to-end framework for assessing hyperkyphosis on routine CT. Unlike traditional Cobb measurements, which require reader input and geometric annotation, muscle–fat% can be extracted directly from volumetric data—automatically, reproducibly, and at scale, requiring only a few seconds of computer time. This transforms CT imaging from a qualitative tool into a quantitative platform for spinal health analytics (see segmentation performance in
Table 2 and voxel-level filtering in
Figure 5). Consistent lower muscle–fat% in the model segmentations compared to manual segmentation appears to reflect superior definition of muscle fat boundaries by the model compared to manual contours by the observers.
Physiologically, the relationship between muscle–fat% and supine kyphosis likely reflects a self-reinforcing cycle: progressive supine kyphosis from muscle weakness leads to decreased activity, promoting further muscle atrophy and fatty infiltration, which in turn reduces postural support and deepens curvature. Quantifying this cycle through a standardized muscle–fat% metric captures the mechanical consequences of spinal imbalance in a way that traditional Cobb angle measurements cannot. The ability to measure muscle–fat% automatically positions it as a scalable surrogate biomarker of sagittal supine curvature—one that complements, and in certain contexts may replace, explicit Cobb measurements for large-scale screening. This can be performed opportunistically on CT scans performed for other purposes as complementary information obtained at negligible additional cost.
4.5. Clinical and Research Implications
From a translational standpoint, automated muscle–fat% quantification has the potential to substantially enhance the impact and value of CT scanning. Potential benefits include opportunistic screening, monitoring, prognosis, precision rehabilitation, and population-scale analytics. Routine thoracoabdominal CT scans performed for a variety of indications could undergo automatic analysis of muscle–fat%, thereby providing additional information on musculoskeletal health that is not currently provided in routine radiology reporting. This assessment of muscle volumes and muscle–fat% is opportunistic because it does not require any additional radiation exposure or exam time for the patient. There is only a minimal, if any, increase in cost for running this automated algorithm, and the outputs could be readily quality-control-checked by radiologists when finalizing their reports.
In patients being assessed for thoracic kyphosis, back pain, and related back disorders, repeated muscle–fat% measurements over time, perhaps annually, could track muscular degeneration or recovery and serve as a quantitative indicator of core muscle health. Measuring the rate of change in muscle volume and muscle–fat% may also help predict future progression, thereby providing prognostic information.
Identifying specific muscles with high muscle–fat% may also create opportunities for therapeutic intervention. Targeting affected muscles or muscle groups with tailored strengthening and conditioning exercises could potentially counteract the observed degenerative pattern or slow its progression. Follow-up imaging could help guide therapeutic adjustments, and in some settings MRI could be used instead of CT to avoid additional radiation exposure.
The standardized nature of the pipeline also allows integration into large datasets for epidemiologic studies of posture, aging, and sarcopenia. Because these metrics can be derived simply and at low incremental cost, large-scale analyses may be practical and cost-effective.
By bridging anatomical, compositional, and geometric features, this pipeline facilitates a more holistic understanding of spinal health.
4.6. Limitations
This cross-sectional study cannot determine the temporal directionality between curvature and muscle degeneration; there is no determination of cause and effect. Also the supine kyphosis cannot be equated to the clinical kyphosis detected on standing X-rays. Muscle–fat% depends on accurate HU calibration and protocol; although we used soft-tissue clipping and a fixed attenuation threshold, variations in scanner model, reconstruction kernel, and patient body habitus may introduce bias. Potential confounders—such as age, body mass index, bone density, socio-economic status and physical activity—were not controlled for in this analysis; however, we were able to identify sex, spine surgery and compression fracture on the CT images to assess for confounding effects. While segmentation accuracy was high overall, small or thin muscles remain susceptible to partial-volume effects, e.g., trapezius which had no significant correlation. (See
Figure 5 for the thresholding approach and
Table 2 for segmentation performance context.) The utility is also limited in patients who are not ambulatory and have developed profound fatty atrophy of the paraspinal muscles. We attempted to eliminate this confounding effect by excluding patients with muscle–fat% > 50 but we did not have access to clinical records that could establish if these subjects were truly non-ambulatory. Although there were patients with minor scoliosis, patients with severe scoliosis or complex spine deformity were also not assessed.
4.7. Future Directions
Future work will include multi-center external segmentation benchmarking to evaluate generalizability across imaging protocols, harmonization of HU thresholds, and covariate-adjusted modeling to disentangle confounding factors. Future research should also perform head-to-head comparisons of the available methods of muscle–fat% quantitation using a range of thresholds and histopathology as the gold standard of reference to determine the best method for measuring intramuscular fatty atrophy in the setting of spinal deformity research. Longitudinal studies will be essential to determine whether baseline muscle–fat% predicts kyphotic progression or functional decline. Integration of muscle–fat% together with automated Cobb angle measurement could create a unified, fully self-contained spine-analysis framework. Ultimately, this approach could enable large-scale, opportunistic screening for hyperkyphosis in the supine position and musculoskeletal degeneration using existing CT archives.




 ,