


Abstract
Background: Assistive technologies (AT) have been used to improve the daily living conditions of people living with dementia (PWD). Research supports the positive impact of the use of AT such as decreased burden on caregivers and behavioral support for people with dementia. Four reviews in the last six years have analyzed AT and PWD, but none have incorporated the dimension of medical outcomes. Objectives: The purpose of this review is to identify the facilitators, barriers, and medical outcomes commensurate with the use of AT with PWD. Method: This review queried The Cumulative Index of Nursing and Allied Health Literature (CINAHL), Web of Science, Science Direct, and PubMed databases for peer-reviewed publications in the last five years for facilitators, barriers, and medical outcomes commensurate with the use of AT with PWD. The study is reported and conducted in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analysis (PRISMA) and the Kruse Protocol for conducting a systematic review. Results: 48 studies were analyzed. Fourteen types of AT, 17 facilitators, 17 barriers, and 16 medical outcomes were identified in the literature. The two most frequently mentioned ATs were cognitive stimulators (9/48, 19%) and social robots (5/48, 10%). The two most frequently mentioned facilitators were caregivers want AT (8/68, 12%) and enables increased independence (7/68, 10%). The top two barriers were cost (8/75, 11%) and PWD reject AT (8/75, 11%). The top medical outcomes were improved cognitive abilities (6/69, 9%), increased activities of daily living (ADLs), and increased autonomy (each at 5/69, 7%): Zero negative outcomes were reported. Conclusion: The systematic review revealed the positive relations that occur when PWD and their caregivers use AT. Although many reservations surrounding the use of AT exist, a majority of the literature shows a positive effect of its use. Research supports a strong support for AT by caregivers due to many positive medical outcomes, but also a reticence to adopt by PWD. If ATs for PWD are a way to reduce stress on caregivers, barriers of cost and complexity need to be addressed through health policy or grants.
1. Introduction
1.1. Rationale
Dementia describes a group of symptoms affecting a person’s cognitive abilities severely enough to interfere with their daily life [1,2]. Currently, over 46 million people live with dementia, and the numbers are expected to increase with the aging of society to 131.5 million by 2025. Dementia is a condition affecting older people and has an impact on families, care givers and society. Commonly, family members are seen to be the care givers to support people with dementia and are usually untrained for this demanding role. The situation, of increasing numbers of those who suffer from dementia combined with an untrained social network to care for them, is rife for a technological intervention.
The etiology and disease stage of dementia patients can be characterized based on their cognitive, behavioral, motor, and functional symptoms [3]. Research supports the incorporation of technology with dementia patients because it plays a role in preventing their cognitive and physical decline. Technological intervention could further propose solutions to the challenges and barriers that limit care in dementia patients [4].
Various technological interventions have been introduced for functions such as of memory support, safety and security for the patient, training for both the caregiver and patient, care delivery, overall treatment, and social interaction [5]. However, barriers to technological treatment, such as privacy concerns, adaptation, and design choice, could result in a decline of the technology’s effectiveness [6]. Assistive technologies for dementia patients vary in their design: for the occasional use of the patient, by the patient, or on the patient (e.g., caregivers) [7]. Technological interventions for dementia patients could provide quality care measures to accommodate daily needs.
Four reviews in the last six years were published. They recognize the rapidly developing world of intelligent assistive technologies (ATs), and attempted to compile comprehensive lists of such devices and their benefit [8,9,10,11]. Date ranges spanned 5–16 years, and the reviewers included studies of both dementia patients and their carers. However, none of these reviews identified the medical outcomes commensurate with the use of AT, which is a basic requirement for a systematic review [12].
1.2. Objectives
The purpose of this review is to compile a current and comprehensive list of facilitators and barriers to the adoption of, and medical outcomes commensurate with, the use of AT by PWD and their carers to perform activities of daily living independently. The results of this review should enable future studies to explore the modifications required for AT to support people with dementia while providing ease of use for the care givers.
2. Methods
2.1. Protocol and Registration
This review followed the Kruse protocol for conducting a systematic review published in 2019 [13], reported in accordance with Preferred Reporting Items for Systematic Reviews and Meta-Analysis (PRISMA) [14]. This review was registered with PROSPERO on 7 May 2020: PROSPERO ID CRD42020182167. In accordance PROSPERO rules, the registration was completed before analysis began.
2.2. Eligibility Criteria
Studies were eligible for this review if participants were diagnosed with dementia or they were care givers (carers) of those with dementia (regardless of stage, gender, race, ethnicity, or age), if the intervention was AT, if they were published in a quality, peer-reviewed journal in the English language in the last five years, and it they report either facilitators to adoption, barriers to adoption, or medical outcomes associated with the use of AT. Five years was chosen due to the rapidly advancing field of AT development. A quality assessment will be performed on each article using the Johns Hopkins Nursing Evidence-Based Practice Rating Scale (JHNEBP) [15]. Any study below IV C will be discarded.
2.3. Information Sources
Reviewers queried four databases: The Cumulative Index of Nursing and Allied Health Literature (CINAHL), PubMed (MEDLINE), Web of Science, and Embase (Science Direct). Databases were filtered for the last five years. Database searches occurred between 1–15 February 2020. We expected to find advances in AT and greater level of adoption of AT due to both availability of these devices and the growing number of PWD. We hoped to find fewer barriers to the adoption of AT for PWD.
2.4. Search
Reviewers initially conducted a search on Google Scholar using general terms. When 10 articles were found on the subject, reviewers collected the key terms from these studies to help form a Boolean search string. Using the PubMed Medical Subject Headings (MeSH), reviewers used the terms gathered from the 10 articles to examine how they were indexed and categorized. Once a Boolean search string was assembled, it was tested out several times in PubMed and customized for maximum, most effective yield. The final search string was (“self-help devices” OR “selfhelp devices” OR “self help devices” OR “assistive technology” OR “telemonitoring” OR “tele-monitoring” telemedicine) AND (dementia OR “cognitive impairment”). We used this same search string for all databases. Reviewers filtered out other reviews and helped the database focus on academic or peer-reviewed journals over the last five years.
2.5. Study Selection
Following the Kruse protocol, reviewers conducted three consensus meetings [13]. The first was to select the group of studies to analyze. Once the search identified a large group to screen, the literature matrix manager downloaded the article details from each research database into an Excel literature matrix which served as the applied form from which to extract data. The group leader assigned workload to the group to ensure all abstracts would be screened by at least two reviewers. Reviewers read their assigned abstracts and screened them against the objective statement making a keep or discard recommendation on the shared spreadsheet. Once all abstracts were screened, the group met to discuss disagreements in recommendations. A final determination was made by the end of the meeting by the group leader, by asking another member of the group to read the abstract. A kappa statistic was calculated based on this process [16].
2.6. Data Collection Process
Once the final group of articles for analysis was identified, the group leader assigned workload to ensure all articles were analyzed by at least two reviewers. Reviewers used the applied form as the data extraction tool to collect Participants, Intervention, Comparison, Outcome, Study design (PICOS) and make general observations. Data items on this spreadsheet were published in the protocol [13]. Reviewers independently analyzed articles, extracting all standardized data items as well as general observations commensurate with the objective statement [13]. At consensus meeting 2, these observations were shared, and a narrative analysis was conducted [17]. The narrative analysis attempts to make sense of the observations. From the observations, common threads were identified. Being mindful of the common threads, or themes, reviewers carefully read their articles another time to flush out additional occurrences. Using the themes, reviewers examined interactions between facilitators, barriers, and medical outcomes to determine if some interventions were more consistently successful or problematic than others.
2.7. Data Items
The applied form collected the following data items: participants, AT intervention, study design, results compared to a control group (where applicable), facilitators and barriers to the use of AT, medical outcomes, sample size, bias within studies, effect size, country of origin, statistics used, a quality assessment from the JHNEBP, and general observations about the article that would help interpret the results [15].
2.8. Risk of Bias within and across Studies
General observations of bias are collected throughout the analysis phase. Bias is discussed in the second consensus meeting along with other observations. Key observations of bias, such as selection bias, are discussed because these could limit the external validity of the results. The JHNEBP was used to assess the risk and quality of each study analyzed. The cumulative evidence from the analysis (selective reporting, etc.) is discussed at the second consensus meeting. The JHNEBP is comprised of five levels for strength of evidence and three levels for quality of evidence. The strength of evidence for level 1 is an experimental study or RCT. Level 2 is strictly for quasi-experimental studies. Level 3 is for non-experimental, qualitative, or meta-synthesis studies. Level 4 is for opinion of nationally recognized experts based on research evidence or consensus panels. Level 5 is for opinions of experts that is not based on research evidence. The quality of evidence is listed as A (high), B (good), or C (low quality or major flaws). Each of these levels contain specifics for research, summative reviews, organizational, and expert opinion. For instance, research in level A must have consistent results with sufficient sample size, adequate control, and definitive conclusions. Research in level B must have reasonably consistent results, sufficient sample size, some control, and definitive conclusions. Research at level C has little evidence with inconsistent results, insufficient sample size, and conclusions that cannot be drawn from the data. Articles with a strength of evidence rating below Level 4 will be screened out. Quality of evidence below level B are highly suspect and must have full consensus of the group to be kept for analysis.
2.9. Summary Measures
The review analyzed studies with qualitative, quantitative, and mixed methods, so the summary measures sought were not consistent. The preferred summary statistic would be the risk ratio, but descriptive statistics and means’ comparisons (student-t) are also sufficient. Summary statistics were discussed at the second consensus meeting.
2.10. Synthesis of Results
This subsection addresses a meta-analysis. This is a systematic review. This section is provided to assure reviewers that PRISMA had been followed. It will be deleted prior to publication, if accepted.
2.11. Additional Analysis
At the second consensus meeting, a narrative analysis will be performed to group observations into themes. These themes will be measured across all articles analyzed and reported in summary statistics in a series of affinity matrices. The narrative analysis summarized themes for facilitators, barriers, and medical outcomes. These will be reported in affinity matrices.
3. Results
3.1. Study Selection
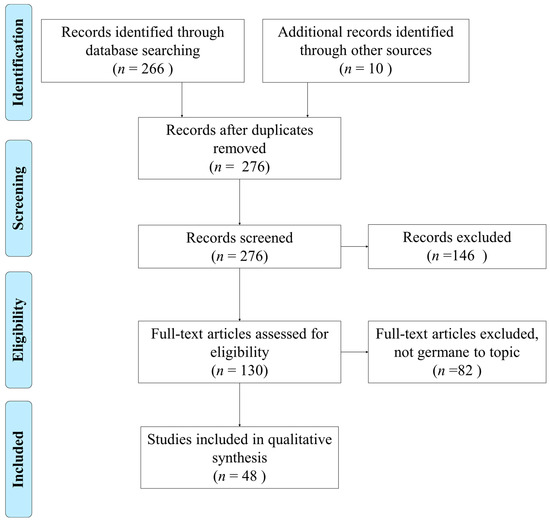
The study selection process performed is illustrated in Figure 1. A kappa statistic was calculated after the first consensus meeting (k = 0.85), which indicates strong agreement [16,18]. After screening, removing duplicates, and assessing for eligibility, the 48 articles chosen for analysis came from CINAHL (16, 33%), Web of Science (16, 33%), PubMed (15, 31%), and Science Direct (1, 2%).
Figure 1.
Preferred Reporting Items for Systematic Reviews and Meta-Analysis (PRISMA) flow diagram of the literature search and selection process.
3.2. Study Characteristics
Using the applied form, reviewers collected several standard items used for summary, such as PICOS. A PICOS table is provided in Table 1. Additional items were collected for analysis, such as forms of AT interventions, facilitators, and barriers to the use of assistive technologies, and the medical outcomes observed from those older adults using AT solutions [13]. These are presented in Table 2. Table 1 and Table 2 lists articles in reverse chronological order: 2019 (4) [3,19,20,21], 2018 (12) [22,23,24,25,26,27,28,29,30,31,32,33], 2017 (14) [34,35,36,37,38,39,40,41,42,43,44,45,46,47], 2016 (11) [48,49,50,51,52,53,54,55,56,57,58], 2015 (7) [59,60,61,62,63,64,65].
Table 1.
PICOS table.
Table 2.
Summary of evidence.
3.3. Risk of Bias within Studies
Reviewers recorded observations of bias at the study level. The most common form of bias was selection bias. Examples of selection bias were all: participants had experience with technology [23], same site [25,28,30,34], or a disproportionately large sample that was male [22,30,36]. These examples of bias limit the external validity of the results.
3.4. Results of Individual Studies
Reviewers collected their observations of intervention and medical outcomes during the analysis phase. The narrative analysis of their observations identified themes. A summary of these themes is listed in Table 1. Repetition in the frame of a theme is due to multiple observations from the same article for that theme. For instance, the theme increased talking comprised observations of “increased utterances” and “increased sustained conversations” [19]. A translation from observations to themes for interventions, medical outcomes, facilitators, and barriers us listed in Table A1, Table A2 and Table A3. Reviewers collected the standard PICOS fields and included them in Table 1. Additional data collected is displayed in Table A4 and Table A5: bias, statistics, country of origin, and quality assessments.
3.5. Synthesis of Results
This subsection addresses meta-analyses. This is a systematic review. This section will be deleted after the review process. It is included to reassure reviewers that we followed the PRISMA checklist.
3.6. Risk of Bias across Studies
Table 3 summarizes the quality indicators identified by the JHNEBP tool [15]. The most prevalent assessment in the strength of evidence (panel a) was level III, followed by I, II, and IV. For quality of evidence (panel b), the most frequently assessed level was level B, followed by A. It is certainly preferable for the strength of evidence to be closer to level I, but that has not resulted from the screening and selection process. This limitation will be addressed later.
Table 3.
Summary of quality assessments.
3.7. Additional Analysis
3.7.1. Interventions of AT
Consensus meeting three identified eight themes and six individual observations that corresponded with AT for PWD. These are listed in Table 4. In the interest of brevity, only the first 60% will be listed. The intervention most often noted was an interview [3,22,23,24,25,29,31,39,43,44,49,57,59,61,63,65]. Researchers interviewed users of AT (PWD and carers) in 16/48 studies (33%). Three of these studies originated in the United Kingdom, two from Norway, two from the Netherlands, and the rest were from single originations: Greece, United States, Pakistan, Finland, Australia, United Kingdom/Italy/Malaysia, Canada, Sweden, and Taiwan. The theme cognitive stimulation (natural language presentation through a Wizard-of-Oz presentation, intelligent cognitive assistant, computerized help information and interaction project, wearable cameras, and evidence-based reasoning and problem solving training) occurred in 9/48 studies (19%) [26,36,37,51,53,54,58,60,65]. Four of these studies originated from the United Kingdom, while the rest were from single originations: France, Scotland, Saudi Arabia, Canada, and Netherlands/Germany/Belgium. Socially assistive robots (artificial intelligence system designed to interact with humans and other robots) were identified in 5/48 studies (10%) [19,35,42,47,62]. These studies all came from single originations: Mexico, Italy/Ireland, Canada, New Zealand, and the United States.
Table 4.
Affinity matrix of ATs.
3.7.2. Facilitators to the Adoption of AT
Fourteen themes and three individual observations were identified as facilitators to the adoption of AT for PWD. These are listed in Table 5. In the interest of brevity, only the top 40% most frequently observed will be reported (other than those not reported). The theme caregivers want AT (AT more ethical than physical barriers, users are open-minded to robotic assistance and sensors, usefulness is high, AT enables PWD to live at home more safely) occurred in 8/68 occurrences (12%) [36,38,39,43,44,47,53,63]. These studies all came from single originations: Australia, Scotland, Canada, United Kingdom, United Kingdom/Italy/Malaysia, Spain, Netherlands, Germany/Belgium, and Taiwan. The theme increased independence (keeps PWD home longer, helps structure everyday events) occurred in 7/68 occurrences (10%) [3,30,40,46,51,53,59]. Three of these studies originated from Sweden, and two were from Canada, while the rest were from single originations: Netherlands, Netherlands/Germany/Belgium. The theme increased safety (increases a sense of security, increases safety) occurred in 6/68 occurrences (9%) [3,25,30,35,41,57]. These studies all came from single originations: Netherlands, Sweden, Norway, United States, New Zealand, and United Kingdom.
Table 5.
Affinity matrix of facilitators to the use of ATs.
3.7.3. Barriers to the Adoption of AT
Eleven themes and six individual observations were identified as barriers to the adoption of AT for PWD. These are listed in Table 6. In the interest of brevity, only the first 50% of the most frequently observed occurrences will be reported (other than those not reported). The theme of cost was identified in 8/75 occurrences (11%) [3,20,35,39,40,52,61]. Two of these studies came from Canada while the rest were from single originations: Netherlands, Australia, New Zealand, Switzerland, and the United Kingdom. The theme PWD do not want AT (PWD reject AT, users do not want a robot, users immediately returned the device, devices are unfamiliar, and participants feel targeted and embarrassed) occurred in 8/75 occurrences (11%) [22,23,24,47,55,62]. Three of these studies originated from the United States, while the others were from single originations: Greece, Canada, Pakistan, Taiwan, and the United Kingdom. The theme complex interfaces (pushing buttons does not always yield the desired result, system was perceived to be complex, complex setup) occurred in 7/75 occurrences (9%) [3,23,25,29,30,51,53]. These studies all came from single originations: Netherlands, Greece, Sweden, Finland, Norway, Canada, Netherlands/Germany/Belgium. The theme development must improve capabilities (false alarms, would only be worn for a few hours due to weight, technical problems, difficult to understand) occurred in 7/75 occurrences (9%) [25,26,29,42,43,48,53]. The theme degenerative nature of dementia complicates the timing of AT used (timing is important – before it is too late, dementia’s progressive nature makes useless today AT that may have been helpful only a short while ago, client’s reduced cognitive and physical abilities greatly reduces the effectiveness of AT more each day) occurred in 7/75 occurrences (9%) [24,25,36,40,42,45,52]. These studies occurred in single originations: Norway, United States, Italy/Ireland, Canada, Scotland, Netherlands, and Switzerland.
Table 6.
Affinity matrix of barriers to the use of ATs.
3.7.4. Medical Outcomes Commensurate with the Adoption of AT
Twelve themes and four individual observations of medical outcomes were recorded commensurate with the adoption of AT. These are listed in Table 7. In the interest of brevity, only the first 40% will be reported. The theme of improved cognitive abilities (reduced sensory loss, increased global cognition, decreased cognitive decline) occurred in 6/69 occurrences (9%) [3,34,56,58,59,60]. Two of these studies originated from the United Kingdom, while the others came from the Netherlands, Australia, Greece, and Sweden. The theme of increased ADLs occurred in 5/69 occurrences (7%) [27,32,44,56,60]. Two of these studies originated from the United Kingdom, while the others came from the United States, Spain, and Greece. The theme of increased autonomy occurred in 5/69 occurrences (7%) [23,25,26,30,59]. Two of these studies originated from Sweden, while the others came from Greece, Norway, and France. The theme of improved memory (helps patients recall past events) occurred in 4/69 occurrences (6%) [34,48,65]. These studies originated from Australia, Sweden, and the United Kingdom. The theme of improved overall health (improved emotional health, improved psychological wellbeing, improved hearing, better tracking of health monitoring through AT) occurred in 4/69 occurrences (6%) [22,33,35,55]. These studies originated from Germany, Pakistan, New Zealand, and the United States. The theme of improved mood (improved emotional wellbeing, improved negative emotions, enabled greater enjoyment) occurred in 4/69 occurrences (6%) [33,34,41,64]. These studies originated from Germany, Australia, British Columbia, and the United States.
Table 7.
Affinity matrix of medical outcomes commensurate with the use of ATs.
3.8. Interactions between Observations
The intervention of eHealth resulted in two instances of increased communication [45,64]. The intervention of cognitive stimulation resulted in two instances of increased independence [51,53]. When researchers interviewed users of AT, there were two instances of PWD do not want AT [22,63] and two instances of increased autonomy [23,25]. The intervention of social robots resulted in two instances of PWD do not want AT [47,62].
4. Discussion
4.1. Summary of Evidence
Fourteen interventions of AT in 48 studies revealed 17 facilitators, 17 barriers, and 16 positive or neutral medical outcomes. The two most frequently mentioned AT were cognitive stimulators (9/48, 19%) and social robots (5/48, 10%). The two most frequently mentioned facilitators were caregivers want AT (8/68, 12%) and enables increased independence (7/68, 10%). The top two barriers were cost (8/75, 11%) and PWD do not want AT (8/75, 11%). The top medical outcomes were improved cognitive abilities (6/69, 9%), increased ADLs, and increased autonomy (each at 5/69, 7%): Zero negative outcomes were reported. Interactions of note occurred with interventions of eHealth and cognitive stimulation, which resulted in multiple observations of increased communication and increased independence, respectively.
Two interesting dichotomies were observed. One study noted no effect in depression, while others noted improved depression [33,41], behavior [24,33,56], mood [33,34,41,64], coping [3,33,62], and decreased stress [25,48]. Also, caregivers want AT [36,38,39,43,44,47,53,63], while PWD do not want AT [22,23,24,47,55,62]. Caregivers feel a sense of relief knowing sensors are in place, and they feel these sensors are more ethical than using physical barriers to prevent elopement, but the complex and foreign nature of the sensors coupled with false alarms cause PWD to reject the same devices that increase their sense of autonomy [23,25,26,30,59].
The observations that AT needs additional development to improve interfaces, reduce false alarms, and improve functionality of devices was no surprise. The challenging aspect to development is seen in the observation that the degenerative nature of AD complicates the timing of AT used. Even the ideal interface, that has been proven effective for a PWD for months, may be obsolete one specific morning due to the degenerative nature of AD, because the PWD may forget how to use it [3,23,52]. Developers might consider AT with phases of simplicity of operation (which might result in reduced capabilities) so that the AT can advance along with the PWD.
Health policy makers should consider augmenting AT development through grants or subsidies. As the aging of society progresses, so will the prevalence of PWD [2]. Development of AT for PWD should be a priority. This corresponds with the theme needs more government involvement.
Social services workers should keep a list of ATs available to PWD at different stages of AD. Caregivers, often spouses or close family, are already experiencing high levels of stress and concern. A general lack of awareness was observed in one study [39]. The combination of more government involvement and funded development should enable such lists to be readily available and regularly updated.
Caregivers should know that AT exists for PWD, and that they are not alone in the struggle to care for their loved ones while also maintaining their own life. AT currently exists, and it improves the quality of life for both PWD and the caregivers [27,32,44,56,60]. The research strongly supports a desire by caregivers for AT. Although a barrier was observed of complex interfaces, several other studies noted the existence AT with simple interfaces with visual and auditory reminders and constant training to control for forgetfulness. Some AT can be provided by the government as part of national health plans.
The findings of this review are commensurate with the other four reviews from the previous six years [8,9,10,11]. The AT reviewed is similar to each of these articles [8]. The decline in memory and cognition is common [9]. One semantic difference is that one review called AT intelligent ATs, and this same review provides an extensive index of AT for clinicians and other stakeholders involved in the management of PWD [10].
The findings in this review are also commensurate with four others from the last year, and the AT reviewed are similar [66,67,68,69,70]. AT interventions can be beneficial to quality of life, social interaction, reducing neuropsychiatric symptoms such as depression, anxiety, and agitation, but continued use of AT becomes problematic due to the progressive nature of dementia [69,70]. Both carers and PWD shared observations on aspects of AT such as ease of use, stability and flexibility of technology, and the importance of privacy and confidentiality [67,68]. One finding that was not in this review was an improvement in pain management, as was found in a review from 2019 [69].
Future research in this area should examine the ethical concerns surrounding AT. If AT yields so many positive medical outcomes, and it is strongly desired by caregivers, why is it also rejected by PWD? Is AT perceived as an annoyance or a bother? Do some view AT as a constraint on liberty? The literature supports the use of AT. It is important for the subject of AT to perceive its value and willingly accept it.
4.2. Limitations
The researchers reviewed papers published between 2015 with 2020 and did not include studies outside this period. One limitation is publication bias for five years. Including some grey literature could have controlled for this limitation. We limited our review to four databases, CINAHL, PubMed, Web of Science, and Science Direct. The intent of including four databases was to mitigate the risk of selection bias. The limitation is that we did not include other databases that might have yielded other articles for consideration.
A team of reviewers determined the articles to be included in the study. This was also done to mitigate the risk of selection bias. The risk of this practice, however, is that the team may have differed in their selection processes. To mitigate this risk, researchers held consensus meetings, identified the research objective, and received multiple reviews for each article. The limitation is that there may not have been enough consensus meetings. The kappa statistic shows the consensus meetings were effective, but a stronger level of agreement is possible.
The assessment of both strength of evidence and quality of evidence was not as high as preferred. The most common strength of evidence was III, while the preference would have been for more level I. To control for this limitation in the future, additional years could have been considered so that more experimental studies or RCTs could have been included in the analysis.
5. Conclusions
The research supports the use of AT with PWD, and many positive or neutral medical outcomes are associated with this practice. This review presents facilitators and barriers associated with the use of AT by PWD, and it presents medical outcomes commensurate with this intervention. It is consistent with other reviews on the same or similar topics. Policy makers and carers should focus on the enablers listed in this review and work to eliminate the barriers to the adoption of AT. Such practice would help policy makers enable additional PWDs and carers to experience the positive aspects of this intervention, for as long as the progressive nature of dementia will allow. Particular focus should be given to helping PWD accept AT based on the positive aspects of their use.
Author Contributions
G.U. was the visualization coordinator and project administrator, who facilitated the project schedule, consensus meetings, milestones, and Figure 1. G.U. analyzed 1/3 of the articles. S.P. was in charge of the literature matrix and tables, and she analyzed 1/3 of articles. K.P. was the editor, to ensure a consistent voice throughout the review, and she analyzed 1/3 of articles. J.F. helped conceptualize the project and analyzed 1/2 of the articles. C.S.K. designed the review, analyzed all articles, and served as senior editor for the project. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Conflicts of Interest
The authors declare no conflict of interest.
Abbreviations
| ADL | activity of daily living |
| ADRD | Alzheimer’s disease and related dementia |
| AMSTAR | assessment of multiple systematic reviews |
| AT | Assistive Technology |
| CCT | Computerized Cognitive Training |
| CT | Cognitive Training |
| CDN | COGKNOW Day Navigator |
| CINAHL | Cumulative Index of Nursing and Allied Health Literature |
| CRDL | (not English) Interactive instrument, developed to stimulate communication between users through sound and touch |
| EPD | Electronic Planning Device |
| GCT | General Cognitive Training |
| ICA | Intelligent cognitive assistants |
| JHNEBP | Johns Hopkins Nursing Evidence-Based Practice rating scale |
| MADRS | Montgomery Asberg’s Depression Rating Scales’ |
| MARIO | Not an abbreviation—just the name of a social robot |
| MCI | Mild Cognitive Impairment |
| MeSH | Medical Subject Heading |
| MMSE | Mini Mental Status Evaluation |
| MrNPS | Mood-related Neuropsychiatric Symptoms |
| NHHI | Nursing Home Hearing Handicap Index |
| PICOS | Participants, Intervention, Comparison (results), Outcomes, Study design |
| PRISMA | Preferred Reporting Items for Systematic Reviews and Meta-Analyses |
| PWD | People with dementia |
| ReaCT | Reasoning and Problem-Solving Cognitive Training |
| ST-CI | Supportive Therapy for Cognitively Impaired Older Adults |
| UCD | User Centered Design |
Key Terms
| Dementia | A progressive, irreversible decline in mental function |
| AT Device | AT device is defined as any item, piece of equipment, or product system whether acquired off the shelf, modified or customized that is used to increase, maintain, or improve functional capabilities of individuals with disabilities. |
| Caregivers or Carers | A caregiver is someone, typically over age 18, who provides care for another. It may be a person who is responsible for the direct care, protection, and supervision of children in a childcare home, or someone who tends to the needs of the elderly or disabled. It is generally one who assists another person who is no longer able to perform the critical tasks of personal or household care necessary for everyday survival. |
Appendix A
Table A1.
Map of Observations for Facilitators to Facilitator Themes.
Table A2.
Map of Observations for Barriers to Barrier Themes.
Table A3.
Map of Observations for Medical Outcomes to Outcome Themes.
Table A4.
Map of Observations for Interventions to Intervention Themes.
Table A5.
Observations of Bias, Country of Origin, Statistics Used, and Quality Assessment.
References
- Lynn, J.D.; Quinn, E.; Rondón-Sulbarán, J.; Ryan, A.; Martin, S.; McCormack, B. A systematic review of electronic assistive technology within supporting living environments for people with dementia. Dementia 2019, 18, 2371–2435. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rathnayake, S.; Moyle, W.; Jones, C.; Calleja, P. mHealth applications as an educational and supportive resource for family carers of people with dementia: An integrative review. Dementia 2019, 18, 3091–3112. [Google Scholar] [CrossRef] [Scilit]
- Kenigsberg, P.A.; Aquino, J.P.; Bérard, A.; Charras, K.; Gzil, F.; Villet, H.; Brémond, F.; Dening, T.; Droës, R.M.; Hicks, B.; et al. Assistive Technologies to Address Capabilities of People with Dementia: From Research to Practice. Dementia 2019, 18, 1568–1595. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Øksnebjerg, L.; Janbek, J.; Woods, B.; Waldemar, G. Assistive technology designed to support self-management of people with dementia: User involvement, dissemination, and adoption. A scoping review. Int. Psychogeriatr. 2019. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lorenz, K.; Freddolino, P.P.; Comas-Herrera, A.; Knapp, M.; Damant, J. Technology-based tools and services for people with dementia and carers: Mapping technology onto the dementia care pathway. Dementia 2019, 18, 725–741. [Google Scholar] [CrossRef] [Scilit]
- Guisado-Fernández, E.; Giunti, G.; Mackey, L.M.; Blake, C.; Caulfield, B.M. Factors Influencing the Adoption of Smart Health Technologies for People With Dementia and Their Informal Caregivers: Scoping Review and Design Framework. JMIR Aging 2019, 2, e12192. [Google Scholar] [CrossRef] [Scilit]
- Ruggiano, N.; Shaw, S.; Bertram, J.; Brown, E.L.; Geldmacher, D.; Clarke, P.; Hristidis, V. The Potential of Information Technology to Navigate Caregiving Systems: Perspectives from Dementia Caregivers. J. Gerontol. Soc. Work 2019, 62, 432–450. [Google Scholar] [CrossRef] [Scilit]
- Evans, J.; Brown, M.; Coughlan, T.; Lawson, G.; Craven, M.P. A Systematic Review of Dementia Focused Assistive Technology. In Human-Computer Interaction: Interaction Technologies, Proceedings of the 17th International Conference, HCI International 2015, Los Angeles, CA, USA, 2–7August, 2015; Springer International Publishing: Cham, Switzerland, 2015; pp. 406–417. [Google Scholar]
- Fleming, R.; Sum, S. Empirical studies on the effectiveness of assistive technology in the care of people with dementia: A systematic review. J. Assist. Technol. 2014, 8, 14–34. [Google Scholar] [CrossRef] [Scilit]
- Ienca, M.; Fabrice, J.; Elger, B.; Wangmo, T.; Caon, M.; Pappagallo, A.S.; Kressig, R.W. Intelligent Assistive Technology for Alzheimer’s Disease and Other Dementias: A Systematic Review. J. Alzheimer’s Dis. 2017, 56, 1301–1340. [Google Scholar] [CrossRef] [Scilit]
- Ienca, M.; Wangmo, T.; Jotterand, F.; Kressig, R.W.; Elger, B. Ethical Design of Intelligent Assistive Technologies for Dementia: A Descriptive Review. Sci. Eng. Ethics 2018, 24, 1035. [Google Scholar] [CrossRef] [Scilit]
- Munn, Z.; Peters, M.D.J.; Stern, C.; Tufanaru, C.; McArthur, A.; Aromataris, E. Systematic review or scoping review? Guidance for authors when choosing between a systematic or scoping review approach. BMC Med. Res. Methodol. 2018, 18, 143. [Google Scholar] [CrossRef] [PubMed]
- Kruse, C.S. Writing a Systematic Review for Publication in a Health-Related Degree Program. JMIR Res. Protoc. 2019, 8, e15490. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- David, M.; Alessandro, L.; Jennifer, T.; Douglas, G.A. Preferred reporting items for systematic reviews and meta-analyses: The PRISMA statement. PLoS Med. 2009, 6, e1000097. [Google Scholar]
- Newhouse, R.P.; Dearholt, S.; Poe, S.; Pugh, L.C.; White, K.M. Organizational Change Strategies for Evidence-Based Practice. Jona J. Nurs. Adm. 2007, 37, 552–557. [Google Scholar] [CrossRef] [Scilit]
- Light, R.J. Measures of response agreement for qualitative data: Some generalizations and alternatives. Psychol. Bull. 1971, 76, 365–377. [Google Scholar] [CrossRef] [Scilit]
- Braun, V.; Clarke, V. Using thematic analysis in psychology. Qual. Res. Psychol. 2006, 3, 77–101. [Google Scholar] [CrossRef] [Scilit]
- McHugh, M.L. Interrater reliability: The kappa statistic. Biochem. Med. 2012, 22, 276–282. [Google Scholar]
- Cruz-Sandoval, D.; Favela, J. Incorporating conversational strategies in a social robot to interact with people with dementia. Dement. Geriatr. Cogn. Disord. 2019, 47, 140–148. [Google Scholar] [CrossRef] [Scilit]
- Czarnuch, S.; Ricciardelli, R.; Mihailidis, A. Informing the development of assistive technologies for persons with dementia by connecting financial measures of wealth to perceptions of task dependence. Technol. Disabil. 2019, 31, 39–49. [Google Scholar] [CrossRef] [Scilit]
- Thomas, N.W.D.; Lindauer, A.; Kaye, J. EVALUATE-AD and Tele-STAR: Novel methodologies for assessment of caregiver burden in a telehealth caregiver intervention - A case study. Dement. Geriatr. Cogn. Disord. 2019, 47, 176–184. [Google Scholar] [CrossRef] [Scilit]
- Asghar, I.; Cang, S.; Yu, H. Usability evaluation of assistive technologies through qualitative research focusing on people with mild dementia. Comput. Hum. Behav. 2018, 79, 192–201. [Google Scholar] [CrossRef] [Scilit]
- Billis, A.; Mantziari, D.; Zilidou, V.; Bamidis, P.D. Co-Creation of an Innovative Vocational Training Platform to Improve Autonomy in the Context of Alzheimer’s Disease. Stud. Health Technol. Inform. 2018, 251, 309–312. [Google Scholar] [PubMed]
- Collins, M.E. Occupational Therapists’ Experience with Assistive Technology in Provision of Service to Clients with Alzheimer’s Disease and Related Dementias. Phys. Occup. Ther. Geriatr. 2018, 36, 179–188. [Google Scholar] [CrossRef] [Scilit]
- Holthe, T.; Jentoft, R.; Arntzen, C.; Thorsen, K. Benefits and burdens: Family caregivers’ experiences of assistive technology (AT) in everyday life with persons with young-onset dementia (YOD). Disabil. Rehabil. Assist. Technol. 2018, 13, 754–762. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jouvelot, P.; Wargnier, P.; Benveniste, S.; Rigaud, A.-S. Usability assessment of interaction management support in LOUISE, an ECA-based user interface for elders with cognitive impairment. Technol. Disabil. 2018, 30, 105–126. [Google Scholar] [CrossRef] [Scilit]
- Lancioni, G.E.; Singh, N.N.; O’Reilly, M.F.; Sigafoos, J.; D’Amico, F.; Laporta, D.; Cattaneo, M.G.; Scordamaglia, A.; Pinto, K. Technology-Based Behavioral Interventions for Daily Activities and Supported Ambulation in People With Alzheimer’s Disease. Am. J. Alzheimer’s Dis. Other Dement. 2018, 33, 318–326. [Google Scholar] [CrossRef] [Scilit]
- Lancioni, G.E.; Singh, N.N.; O’Reilly, M.F.; Sigafoos, J.; D’Amico, F.; Pinto, K.; De Vanna, F.; Caffò, A.O. Promoting supported ambulation in persons with advanced Alzheimer’s disease: A pilot study. Disabil. Rehabil. Assist. Technol. 2018, 13, 101–106. [Google Scholar] [CrossRef] [Scilit]
- Nauha, L.; Keranen, N.S.; Kangas, M.; Jamsa, T.; Reponen, J. Assistive technologies at home for people with a memory disorder. Dementia 2018, 17, 909–923. [Google Scholar] [CrossRef] [Scilit]
- Olsson, A.; Persson, A.-C.; Bartfai, A.; Boman, I.-L. Sensor technology more than a support. Scand. J. Occup. Ther. 2018, 25, 79–87. [Google Scholar] [CrossRef] [Scilit]
- Thoma-Lürken, T.; Bleijlevens, M.H.C.; Lexis, M.A.S.; de Witte, L.P.; Hamers, J.P.H. Facilitating aging in place: A qualitative study of practical problems preventing people with dementia from living at home. Geriatr. Nurs. 2018, 39, 29–38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Valdivieso, B.; García-Sempere, A.; Sanfélix-Gimeno, G.; Faubel, R.; Librero, J.; Soriano, E.; Peiró, S. The effect of telehealth, telephone support or usual care on quality of life, mortality and healthcare utilization in elderly high-risk patients with multiple chronic conditions. A prospective study. Med. Clin. 2018, 151, 308–314. [Google Scholar] [CrossRef] [Scilit]
- Wilz, G.; Reder, M.; Meichsner, F.; Soellner, R. The Tele.TAnDem Intervention: Telephone-based CBT for Family Caregivers of People with Dementia. Gerontologist 2018, 58, e118–e129. [Google Scholar] [CrossRef] [Scilit]
- Bahar-Fuchs, A.; Webb, S.; Bartsch, L.; Clare, L.; Rebok, G.; Cherbuin, N.; Anstey, K.J. Tailored and Adaptive Computerized Cognitive Training in Older Adults at Risk for Dementia: A Randomized Controlled Trial. J. Alzheimers Dis. 2017, 60, 889–911. [Google Scholar] [CrossRef] [Scilit]
- Darragh, M.; Ahn, H.S.; MacDonald, B.; Liang, A.; Peri, K.; Kerse, N.; Broadbent, E. Homecare Robots to Improve Health and Well-Being in Mild Cognitive Impairment and Early Stage Dementia: Results From a Scoping Study. J. Am. Med. Dir. Assoc. 2017, 18, 1099.e1091–1099.e1094. [Google Scholar] [CrossRef] [Scilit]
- Dethlefs, N.; Milders, M.; Cuayáhuitl, H.; Al-Salkini, T.; Douglas, L. A natural language-based presentation of cognitive stimulation to people with dementia in assistive technology: A pilot study. Inform. Health Soc. Care 2017, 42, 349–360. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fardoun, H.M.; Mashat, A.A.; Ramirez Castillo, J. Recognition of familiar people with a mobile cloud architecture for Alzheimer patients. Disabil. Rehabil. 2017, 39, 398–402. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garzón-Maldonado, F.J.; Gutiérrez-Bedmar, M.; Serrano-Castro, V.; Requena-Toro, M.V.; Padilla-Romero, L.; García-Casares, N. An assessment of telephone assistance systems for caregivers of patients with Alzheimer disease. Neurol. Engl. Ed. 2017, 32, 595–601. [Google Scholar] [CrossRef] [Scilit]
- Jarvis, F.; Clemson, L.M.; Mackenzie, L. Technology for dementia: Attitudes and practices of occupational therapists in providing assistive technology for way finding. Disabil. Rehabil. Assist. Technol. 2017, 12, 373–377. [Google Scholar] [CrossRef] [Scilit]
- Jiancaro, T.; Jaglal, S.B.; Mihailidis, A. Technology, design and dementia: An exploratory survey of developers. Disabil. Rehabil. Assist. Technol. 2017, 12, 573–584. [Google Scholar] [CrossRef] [Scilit]
- Kiosses, D.N.; Gross, J.J.; Banerjee, S.; Duberstein, P.R.; Putrino, D.; Alexopoulos, G.S. Negative Emotions and Suicidal Ideation during Psychosocial Treatments in Older Adults with Major Depression and Cognitive Impairment. Am. J. Geriatr. Psychiatry 2017, 25, 620–629. [Google Scholar] [CrossRef] [Scilit]
- Kouroupetroglou, C.; Casey, D.; Raciti, M.; Barrett, E.; D’Onofrio, G.; Ricciardi, F.; Giuliani, F.; Greco, A.; Sancarlo, D.; Mannion, A.; et al. Interacting with Dementia: The MARIO Approach. Stud. Health Technol. Inform. 2017, 242, 38–47. [Google Scholar] [PubMed]
- Me, R.C.; Andreoni, G.; Biamonti, A.; Mohd Saad, M.R. Wearable haptic-feedback navigational assistance for people with dementia: Preliminary assessment. Technol. Disabil. 2017, 29, 35–46. [Google Scholar] [CrossRef] [Scilit]
- Soilemezi, D.; Kallitsis, P.; Drahota, A.; Crossland, J.; Stores, R.; Costall, A. The Impact of the Physical Home Environment for Family Carers of People with Dementia: A Qualitative Study. J. Hous. Elder. 2017, 31, 303–333. [Google Scholar] [CrossRef] [Scilit]
- Teunissen, L.; Luyten, T.; de Witte, L. Reconnecting People with Dementia by Using the Interactive Instrument CRDL. Stud. Health Technol. Inform. 2017, 242, 9–15. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Toots, A.; Littbrand, H.; Holmberg, H.; Nordström, P.; Lundin-Olsson, L.; Gustafson, Y.; Rosendahl, E. Walking Aids Moderate Exercise Effects on Gait Speed in People With Dementia: A Randomized Controlled Trial. J. Am. Med. Dir. Assoc. 2017, 18, 227–233. [Google Scholar] [CrossRef] [Scilit]
- Wang, R.H.; Sudhama, A.; Begum, M.; Huq, R.; Mihailidis, A. Robots to assist daily activities: Views of older adults with Alzheimer’s disease and their caregivers. Int. Psychogeriatr. 2017, 29, 67–79. [Google Scholar] [CrossRef] [Scilit]
- Adolfsson, P.; Lindstedt, H.; Pettersson, I.; Hermansson, L.N.; Janeslätt, G. Perception of the influence of environmental factors in the use of electronic planning devices in adults with cognitive disabilities. Disabil. Rehabil. Assist. Technol. 2016, 11, 493–500. [Google Scholar] [CrossRef] [Scilit]
- Arntzen, C.; Holthe, T.; Jentoft, R. Tracing the successful incorporation of assistive technology into everyday life for younger people with dementia and family carers. Dementia 2016, 15, 646–662. [Google Scholar] [CrossRef] [Scilit]
- Boger, J.; Taati, B.; Mihailidis, A. Interdisciplinary development of manual and automated product usability assessments for older adults with dementia: Lessons learned. Disabil. Rehabil. Assist. Technol. 2016, 11, 581–587. [Google Scholar] [CrossRef] [Scilit]
- Czarnuch, S.; Mihailidis, A. Development and evaluation of a hand tracker using depth images captured from an overhead perspective. Disabil. Rehabil. Assist. Technol. 2016, 11, 150–157. [Google Scholar] [CrossRef] [Scilit]
- Egan, K.J.; Pot, A.M. Encouraging Innovation for Assistive Health Technologies in Dementia: Barriers, Enablers and Next Steps to Be Taken. J. Am. Med. Dir. Assoc. 2016, 17, 357–363. [Google Scholar] [CrossRef] [Scilit]
- Hattink, B.J.; Meiland, F.J.; Overmars-Marx, T.; de Boer, M.; Ebben, P.W.; van Blanken, M.; Verhaeghe, S.; Stalpers-Croeze, I.; Jedlitschka, A.; Flick, S.E.; et al. The electronic, personalizable Rosetta system for dementia care: Exploring the user-friendliness, usefulness and impact. Disabil. Rehabil. Assist. Technol. 2016, 11, 61–71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jawaid, S.B.; McCrindle, R. Computerised help information and interaction project for people with memory loss and mild dementia. Int. J. Pain Manag. 2016, 9, 265–275. [Google Scholar]
- Jupiter, T. Does Hearing Assistive Technology Provide Benefit to Nursing Home Residents with Dementia? A Pilot Study. J. Acad. Rehabil. Audiol. 2016, 49, 34–39. [Google Scholar]
- Lazarou, I.; Karakostas, A.; Stavropoulos, T.G.; Tsompanidis, T.; Meditskos, G.; Kompatsiaris, I.; Tsolaki, M. A Novel and Intelligent Home Monitoring System for Care Support of Elders with Cognitive Impairment. J. Alzheimer’s Dis. 2016, 54, 1561–1591. [Google Scholar] [CrossRef] [Scilit]
- Newton, L.; Dickinson, C.; Gibson, G.; Brittain, K.; Robinson, L. Exploring the views of GPs, people with dementia and their carers on assistive technology: A qualitative study. BMJ Open 2016, 6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wolters, M.K.; Kelly, F.; Kilgour, J. Designing a spoken dialogue interface to an intelligent cognitive assistant for people with dementia. Health Inform. J 2016, 22, 854–866. [Google Scholar] [CrossRef] [Scilit]
- Adolfsson, P.; Lindstedt, H.; Janeslätt, G. How people with cognitive disabilities experience electronic planning devices. NeuroRehabilitation 2015, 37, 379–392. [Google Scholar] [CrossRef] [Scilit]
- Corbett, A.; Owen, A.; Hampshire, A.; Grahn, J.; Stenton, R.; Dajani, S.; Burns, A.; Howard, R.; Williams, N.; Williams, G.; et al. The Effect of an Online Cognitive Training Package in Healthy Older Adults: An Online Randomized Controlled Trial. J. Am. Med. Dir. Assoc. 2015, 16, 990–997. [Google Scholar] [CrossRef] [Scilit]
- Gibson, G.; Dickinson, C.; Brittain, K.; Robinson, L. The everyday use of assistive technology by people with dementia and their family carers: A qualitative study. BMC Geriatr. 2015, 15, 89. [Google Scholar] [CrossRef] [Scilit]
- Kerssens, C.; Kumar, R.; Adams, A.E.; Knott, C.C.; Matalenas, L.; Sanford, J.A.; Rogers, W.A. Personalized technology to support older adults with and without cognitive impairment living at home. Am. J. Alzheimer’s Dis. Other Demen. 2015, 30, 85–97. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mao, H.F.; Chang, L.H.; Yao, G.; Chen, W.Y.; Huang, W.N. Indicators of perceived useful dementia care assistive technology: Caregivers’ perspectives. Geriatr. Gerontol. Int. 2015, 15, 1049–1057. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Purves, B.A.; Phinney, A.; Hulko, W.; Puurveen, G.; Astell, A.J. Developing CIRCA-BC and exploring the role of the computer as a third participant in conversation. Am. J. Alzheimers Dis. Other Demen. 2015, 30, 101–107. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Woodberry, E.; Browne, G.; Hodges, S.; Watson, P.; Kapur, N.; Woodberry, K. The use of a wearable camera improves autobiographical memory in patients with Alzheimer’s disease. Memory 2015, 23, 340–349. [Google Scholar] [CrossRef] [Scilit]
- Boger, J.; Jackson, P.; Mulvenna, M.; Sixsmith, J.; Sixsmith, A.; Mihailidis, A.; Kontos, P.; Miller Polgar, J.; Grigorovich, A.; Martin, S. Principles for fostering the transdisciplinary development of assistive technologies. Disabil. Rehabil. Assist. Technol. 2017, 12, 480–490. [Google Scholar] [CrossRef] [Scilit]
- Rondon-Sulbaran, J.; Daly-Lynn, J.; Martin, S.; McCormack, B.; Ryan, A. An exploration of the experiences of informal carers supporting a relative living with dementia during and after the move to technology-enriched supported accommodation. Ageing Soc. 2019. [Google Scholar] [CrossRef] [Scilit]
- Van Boekel, L.C.; Wouters, E.J.M.; Grimberg, B.M.; van der Meer, N.J.M.; Luijkx, K.G. Perspectives of Stakeholders on Technology Use in the Care of Community-Living Older Adults with Dementia: A Systematic Literature Review. Healthcare 2019, 7, 73. [Google Scholar]
- Kang, H.S.; Makimoto, K.; Konno, R.; Koh, I.S. Review of outcome measures in PARO robot intervention studies for dementia care. Geriatr. Nurs. 2020, 41, 207–214. [Google Scholar] [CrossRef] [Scilit]
- Sriram, V.; Jenkinson, C.; Peters, M. Carers’ experience of using assistive technology for dementia care at home: A qualitative study. BMJ Open 2020, 10. [Google Scholar] [CrossRef] [Scilit]

© 2020 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).