AI-Driven Microcalcification Detection in Digital Mammography for Early Breast Cancer Diagnosis: A Scoping Review, Challenges, Limitations, and Future Perspectives

 ,


 ,
 and
Abstract
1. Introduction
Distinction from Prior Reviews
- Comparative analysis of detection methods: A review of DL, ML, and rule-based approaches for the detection of MCs and MCCs, highlighting their performance, limitations, and clinical applicability.
- Explainability in clinical AI systems: An analysis of the role of XAI techniques in enhancing interpretability, radiologists’ trust, and workflow integration in AI-assisted mammography systems.
- Data-centric challenges and solutions: A review of synthetic data generation techniques to mitigate challenges posed by limited, imbalanced, or privacy-constrained datasets, and their impact on model robustness, reduction in dataset bias, and generalizability across heterogeneous clinical settings.
2. Methodology
2.1. Search Strategy
2.2. Selection Process
2.3. Risk of Bias
- Study Design: Retrospective analysis, prospective validation, or comparative bench-marking.
- Data Source: Public versus private datasets; screening versus diagnostic data.
- Validation Strategy: Internal validation (e.g., cross-validation) or external validation on independent datasets.
- Reference Standard: Method used to establish the ground truth (e.g., biopsy confirmation, expert radiologist consensus).
2.4. Data Extraction
- Bibliographic Information: Authors, publication year, and study title.
- Study Characteristics: Primary task (detection, segmentation, classification, or diagnosis), methodological approach, and specific algorithm(s) used.
- Dataset Information: Name and type of dataset(s) used (e.g., INbreast, DDSM), number of images or cases, and key dataset characteristics mentioned.
- Key Findings: Main outcomes, reported performance metrics (e.g., sensitivity, specificity, AUC), and principal conclusions.
- Limitations and Future Work: Challenges, limitations, and suggested future directions reported by the study authors.
2.5. Data Synthesis
- Evolution of Technical Approaches: Charting the progression from visual inspection and rule-based systems to traditional ML and contemporary DL architectures.
- Data Ecosystem and Its Influence: Analyzing the role, characteristics, and reported limitations of datasets used in model development and validation.
- Reported Challenges and Limitations: Synthesizing the technical, clinical, and translational barriers identified across the literature.
- Emerging Trends and Proposed Solutions: Collating future directions and novel approaches proposed by researchers.
2.6. Data Presentation and Summary
- Summary tables (e.g., Table 8) are used to present comparative overviews of key concepts.
- Descriptive statistics (e.g., counts and percentages of studies by methodology type) are provided where they meaningfully illustrate the scope of the evidence.
- The narrative integrates direct findings from the extracted data to describe the state of the field, identify consensus points, and highlight areas of contradiction or evidence gaps.
3. Why MC Detection Remains Challenging: A Clinical Perspective
3.1. Morphological and Distributional Complexity
3.2. Technical Imaging Factors
3.3. Breast Density and Anatomical Overlap
3.4. Human Factors
4. MC Detection Methods
4.1. Visual Inspection
4.2. Rule-Based Systems
4.3. Machine Learning-Based Methods
5. The Role of the Datasets
6. Challenges and Limitations
7. Synthesis of Research Questions
8. Risk of Bias Due to Missing Results
9. Certainty of Evidence and Sensitivity Analyses
10. Future Directions and Conclusions
10.1. Future Directions
10.2. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
Abbreviations
| 3D | Three Dimensional |
| AdaBoost | Adaptive Boosting |
| AI | Artificial Intelligence |
| ANN | Artificial Neural Network |
| AUC | Area Under the Curve |
| BCDR | Breast Cancer Digital Repository |
| BI-RADS | Breast Imaging-Reporting and Data System |
| CAD | Computer-Aided Detection |
| CBIS-DDSM | Curated Breast Imaging Subset of DDSM |
| CC | Craniocaudal |
| cGAN | Conditional Generative Adversarial Networks |
| CNN | Convolutional Neural Network |
| DCIS | Ductal Carcinoma In Situ |
| DDSM | Digital Database for Screening Mammography |
| DICOM | Digital Imaging and Communications in Medicine |
| DL | Deep Learning |
| DT | Decision Tree |
| EMBED | The Emory Breast Imaging Dataset |
| FFDM | Full-Field Digital Mammography |
| FID | Fréchet Inception Distance |
| FN | False Negative |
| FP | False Positive |
| FPR | False Positive Rate |
| FROC | Free-Response Receiver Operating Characteristic |
| GAN | Generative Adversarial Network |
| GLCM | Gray-Level Co-occurrence Matrix |
| GLRLM | Gray-Level Run-Length Matrix |
| Grad-CAM | Gradient-weighted Class Activation Mapping |
| GRADE | Grading of Recommendations Assessment, Development and Evaluation |
| HSAM | Hierarchical Spatial Attention Module |
| IARC | International Agency for Research on Cancer |
| IDC | Invasive Ductal Carcinoma |
| k-NN | k-Nearest Neighbors |
| LRM | Linear Regression Model |
| mAP | Mean Average Precision |
| MC | Microcalcification |
| MCC | Microcalcification Cluster |
| MIAS | Mammographic Image Analysis Society |
| ML | Machine Learning |
| MLO | Mediolateral Oblique |
| MLP | Multilayer Perceptron |
| NN | Neural Networks |
| NB | Naive Bayes |
| PCA | Principal Component Analysis |
| PIQE | Perception-based Image Quality Evaluator |
| PPV | Positive Predictive Value |
| PRISMA | Preferred Reporting Items for Systematic Reviews and Meta-Analyses |
| PRISMA-ScR | Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews |
| PROSPERO | International Prospective Register of Systematic Reviews |
| QUADAS-2 | Quality Assessment of Diagnostic Accuracy Studies (version 2) |
| RF | Random Forest |
| ROC | Receiver Operating Characteristic |
| SFM | Screen-Film Mammography |
| SHAP | SHapley Additive exPlanations |
| SPICE | Setting, Perspective, Intervention, Comparison, Evaluation |
| SSIM | Structural Similarity Index |
| SVM | Support Vector Machine |
| VAE | Variational Autoencoder |
| VQ | Vector Quatization |
| VQ-VAE | Vector-Quantized Variational Autoencoder |
| WT | Wavelet Transform |
| XAI | Explainable Artificial Intelligence |
| XGBoost | eXtreme Gradient Boosting |
| YOLO | You Only Look Once |
References
- American Cancer Society. About Breast Cancer; Technical Report; American Cancer Society: Atlanta, GA, USA, 2024; Available online: https://www.cancer.org/content/dam/CRC/PDF/Public/8577.00.pdf (accessed on 2 June 2026).
- Mosquera, I.; Barajas, C.B.; Theriault, H.; Benitez Majano, S.; Zhang, L.; Maza, M.; Luciani, S.; Carvalho, A.L.; Basu, P. Assessment of Barriers to Cancer Screening and Interventions Implemented to Overcome These Barriers in 27 Latin American and Caribbean Countries. Int. J. Cancer 2024, 155, 719–730. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Siegel, R.L.; Giaquinto, A.N.; Jemal, A. Cancer statistics, 2024. CA Cancer J. Clin. 2024, 74, 12–49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonfiglio, R.; Scimeca, M.; Urbano, N.; Bonanno, E.; Schillaci, O. Breast Microcalcifications: Biological and Diagnostic Perspectives. Future Oncol. 2018, 14, 3097–3099. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Destounis, S.V.; Friedewald, S.M.; Grimm, L.J.; Poplack, S.P.; Sung, J.S. Mammography. In ACR BI-RADS® Atlas, Breast Imaging Reporting and Data System, v2025 ed.; American College of Radiology: Reston, VA, USA, 2025. [Google Scholar]
- Logullo, A.F.; Prigenzi, K.C.; Nimir, C.C.; Franco, A.F.; Campos, M.S. Breast Microcalcifications: Past, Present and Future (Review). Mol. Clin. Oncol. 2022, 16, 81. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basile, T.M.A.; Fanizzi, A.; Losurdo, L.; Bellotti, R.; Bottigli, U.; Dentamaro, R.; Didonna, V.; Fausto, A.; Massafra, R.; Moschetta, M.; et al. Microcalcification Detection in Full-Field Digital Mammograms: A Fully Automated Computer-Aided System. Phys. Medica 2019, 64, 1–9. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Selmouni, F.; Bendahhou, K.; Sauvaget, C.; Abahssain, H.; Lucas, E.; Muwonge, R.; Mimouni, H.; Ismaili, R.; Bidar, S.; Benkaddour, F.Z.; et al. Impact of Clinical Breast Examination-Based Screening Program on Care Pathway, Stage at Diagnosis, Nature of Treatment, and Overall Survival Among Breast Cancer Patients in Morocco. Cancer 2024, 130, 3353–3363. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fadil, R.; Jackson, A.; El Majd, B.A.; El Ghazi, H.; Kaabouch, N. Classification of Microcalcifications in Mammograms using 2D Discrete Wavelet Transform and Random Forest. In Proceedings of the 2020 IEEE International Conference on Electro Information Technology (EIT), Chicago, IL, USA, 31 July 2020–1 August 2020; pp. 353–359. [Google Scholar] [CrossRef] [Scilit]
- Hernández-Vázquez, A.; Hernández-Rodríguez, Y.; Cortes-Rojas, F.; Bayareh-Mancilla, R.; Cigarroa-Mayorga, O. Automated Mammogram Analysis for Microcalcification Identification using Convolutional Neural Networks. In Proceedings of the XLVII Mexican Conference on Biomedical Engineering; Springer: Cham, Switzerland, 2025; pp. 113–123. [Google Scholar] [CrossRef] [Scilit]
- Luna Lozoya, R.S.; Ochoa Domínguez, H.d.J.; Sossa Azuela, J.H.; Cruz Sánchez, V.G.; Vergara Villegas, O.O. Residual Shallow Convolutional Neural Network to Classify Microcalcification Clusters in Digital Mammograms. Biomed. Signal Process. Control 2025, 102, 107209. [Google Scholar] [CrossRef] [Scilit]
- Fisches, Z.V.; Ball, M.; Mukama, T.; Štih, V.; Payne, N.R.; Hickman, S.E.; Gilbert, F.J.; Bunk, S.; Leibig, C. Strategies for Integrating Artificial Intelligence into Mammography Screening Programmes: A Retrospective Simulation Analysis. Lancet Digit. Health 2024, 6, e803–e814. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qureshi, S.A.; Aziz-Ul-Rehman; Hussain, L.; Sadiq, T.; Shah, S.T.H.; Mir, A.A.; Nadim, M.A.; Williams, D.K.A.; Duong, T.Q.; Chaudhary, Q.U.A.; et al. Breast Cancer Detection using Mammography: Image Processing to Deep Learning. IEEE Access 2025, 13, 60776–60801. [Google Scholar] [CrossRef] [Scilit]
- Bashir, N.; Bhosle, N. Deep Learning Driven Multi-Modal Breast Cancer Detection for Early and Accurate Diagnosis. J. Inf. Syst. Eng. Manag. 2026, 11, 799–808. [Google Scholar] [CrossRef]
- Añez, D.; Conti, G.; Uriarte, J.J.; Serrano-Olmedo, J.J.; Martínez-Murillo, R.; Casanova-Carvajal, O. Artificial Intelligence Pipeline for Mammography-Based Breast Cancer Detection: An Integrated Systematic Review and Large-Scale Experimental Validation. Medicina 2025, 61, 2237. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Leeuwen, M.M.; Doyle, S.; van den Belt-Dusebout, A.W.; van der Mierden, S.; Loo, C.E.; Mann, R.M.; Teuwen, J.; Wesseling, J. Clinicopathological and Prognostic Value of Calcification Morphology Descriptors in Ductal Carcinoma In Situ of the Breast: A Systematic Review and Meta-Analysis. Insights Imaging 2023, 14, 213. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMA-ScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 Statement: An Updated Guideline for Reporting Systematic Reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Haddaway, N.R.; Page, M.J.; Pritchard, C.C.; McGuinness, L.A. PRISMA2020: An R Package and Shiny App for Producing PRISMA 2020-Compliant Flow Diagrams, with Interactivity for Optimised Digital Transparency and Open Synthesis. Campbell Syst. Rev. 2022, 18, e1230. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alavudeen Basha, A.; Vivekanandan, S.; Mubarakali, A.; Alqahtani, A.S. Enhanced Mam- mogram Classification with Convolutional Neural Network: An Improved Algorithm for Automated Breast Cancer Detection. Measurement 2023, 221, 113551. [Google Scholar] [CrossRef] [Scilit]
- Chan, H.P.; Helvie, M.A.; Gao, M.; Hadjiiski, L.; Zhou, C.; Garver, K.; Klein, K.A.; McLaughlin, C.; Oudsema, R.; Rahman, W.T.; et al. Deep Learning Denoising of Digital Breast Tomosynthesis: Observer Performance Study of the Effect on Detection of Microcalcifications in Breast Phantom Images. Med. Phys. 2023, 50, 6177–6189. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nissan, N.; Ochoa Albiztegui, R.E.; Fruchtman-Brot, H.; Gluskin, J.; Arita, Y.; Amir, T.; Reiner, J.S.; Feigin, K.; Mango, V.L.; Jochelson, M.S.; et al. Extremely Dense Breasts: A Comprehensive Review of Increased Cancer Risk and Supplementary Screening Methods. Eur. J. Radiol. 2025, 182, 111837. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bazira, P.J.; Ellis, H.; Mahadevan, V. Anatomy and Physiology of the Breast. Surgery 2022, 40, 79–83. [Google Scholar] [CrossRef] [Scilit]
- Stec, N.; Arje, D.; Moody, A.R.; Krupinski, E.A.; Tyrrell, P.N. A Systematic Review of Fatigue in Radiology: Is It a Problem? Am. J. Roentgenol. 2018, 210, 799–806. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lång, K.; Josefsson, V.; Larsson, A.M.; Larsson, S.; Högberg, C.; Sartor, H.; Hofvind, S.; Andersson, I.; Rosso, A. Artificial Intelligence-Supported Screen Reading Versus Standard Double Reading in the Mammography Screening with Artificial Intelligence Trial (MASAI): A Clinical Safety Analysis of a Randomised, Controlled, Non-Inferiority, Single-Blinded, Screening Accuracy Study. Lancet Oncol. 2023, 24, 936–944. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lai, Y.C.; Ray, K.M.; Lee, A.Y.; Hayward, J.H.; Freimanis, R.I.; Lobach, I.V.; Joe, B.N. Microcalcifications Detected at Screening Mammography: Synthetic Mammography and Digital Breast Tomosynthesis versus Digital Mammography. Radiology 2018, 289, 630–638. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bahl, M.; Kshirsagar, A.; Pohlman, S.; Lehman, C.D. Traditional Versus Modern Approaches to Screening Mammography: A Comparison of Computer-Assisted Detection for Synthetic 2D Mammography Versus an Artificial Intelligence Algorithm for Digital Breast Tomosynthesis. Breast Cancer Res. Treat. 2025, 210, 529–537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dembrower, K.E.; Crippa, A.; Eklund, M.; Strand, F. Human-AI Interaction in the Screen-TrustCAD Trial: Recall Proportion and Positive Predictive Value Related to Screening Mammograms Flagged by AI CAD versus a Human Reader. Radiology 2025, 314, e242566. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karale, V.A.; Ebenezer, J.P.; Chakraborty, J.; Singh, T.; Sadhu, A.; Khandelwal, N.; Mukhopadhyay, S. A Screening CAD Tool for the Detection of Microcalcification Clusters in Mammograms. J. Digit. Imaging 2019, 32, 728–745. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lamb, L.R.; Lehman, C.D.; Gastounioti, A.; Conant, E.F.; Bahl, M. Artificial Intelligence (AI) for Screening Mammography, From the AJR Special Series on AI Applications. Am. J. Roentgenol. 2022, 219, 369–380. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morgan, M.B.; Mates, J.L. Applications of Artificial Intelligence in Breast Imaging. Radiol. Clin. N. Am. 2021, 59, 139–148. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Taylor, C.R.; Monga, N.; Johnson, C.; Hawley, J.R.; Patel, M. Artificial Intelligence Applications in Breast Imaging: Current Status and Future Directions. Diagnostics 2023, 13, 2041. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheng, H.D.; Cai, X.; Chen, X.; Hu, L.; Lou, X. Computer-Aided Detection and Classification of Microcalcifications in Mammograms: A Survey. Pattern Recognit. 2003, 36, 2967–2991. [Google Scholar] [CrossRef] [Scilit]
- Suckling, J.; Parker, J.; Dance, D.; Astley, S.; Hutt, I.; Boggis, C.; Ricketts, I.; Stamatakis, E.; Cerneaz, N.; Kok, S.; et al. The Mammographic Image Analysis Society Digital Mammogram Database. In Proceedings of the 2nd International Workshop on Digital Mammography; Elsevier Science: New York, NY, USA, 1994; pp. 375–378. [Google Scholar]
- Alasadi, A.H.H.; Al-Saedi, A.K.H. A Method for Microcalcifications Detection in Breast Mammograms. J. Med. Syst. 2017, 41, 68. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ciecholewski, M. Microcalcification Segmentation from Mammograms: A Morphological Approach. J. Digit. Imaging 2017, 30, 172–184. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Papadopoulos, A.; Fotiadis, D.I.; Costaridou, L. Improvement of Microcalcification Cluster Detection in Mammography Utilizing Image Enhancement Techniques. Comput. Biol. Med. 2008, 38, 1045–1055. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Al-Qdah, M.; Ramli, A.R.; Mahmud, R. A System of Microcalcifications Detection and Evaluation of the Radiologist: Comparative Study of the Three Main Races in Malaysia. Comput. Biol. Med. 2005, 35, 905–914. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arodź, T.; Kurdziel, M.; Popiela, T.J.; Sevre, E.O.D.; Yuen, D.A. Detection of Clustered Microcalcifications in Small-Field Digital Mammography. Comput. Methods Programs Biomed. 2006, 81, 56–65. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Destounis, S.V.; DiNitto, P.; Logan-Young, W.; Bonaccio, E.; Zuley, M.L.; Willison, K.M. Can Computer-Aided Detection with Double Reading of Screening Mammograms Help Decrease the False-Negative Rate? Initial Experience. Radiology 2004, 232, 578–584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fanizzi, A.; Tangaro, S.; Bellotti, R.; Basile, T.M.A.; Bottigli, U.; Losurdo, L.; Massafra, R.; Tamborra, P.; Didonna, V.; La Forgia, D. Automatised Detection of Microcalcification in Mammography. Phys. Medica 2016, 32, 217. [Google Scholar] [CrossRef] [Scilit]
- Halkiotis, S.; Botsis, T.; Rangoussi, M. Automatic Detection of Clustered Microcalcifications in Digital Mammograms using Mathematical Morphology and Neural Networks. Signal Process. 2007, 87, 1559–1568. [Google Scholar] [CrossRef] [Scilit]
- Linguraru, M.G.; Marias, K.; English, R.; Brady, M. A Biologically Inspired Algorithm for Microcalcification Cluster Detection. Med. Image Anal. 2006, 10, 850–862. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ge, J.; Hadjiiski, L.M.; Sahiner, B.; Wei, J.; Helvie, M.A.; Zhou, C.; Chan, H.P. Computer-Aided Detection System for Clustered Microcalcifications: Comparison of Performance on Full-Field Digital Mammograms and Digitized Screen-Film Mammograms. Phys. Med. Biol. 2007, 52, 981–1000. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malar, E.; Kandaswamy, A.; Chakravarthy, D.; Giri Dharan, A. A Novel Approach for Detection and Classification of Mammographic Microcalcifications using Wavelet Analysis and Extreme Learning Machine. Comput. Biol. Med. 2012, 42, 898–905. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mohanalin, J.; Beena Mol, M. A New Wavelet Algorithm to Enhance and Detect Microcalcifications. Signal Process. 2014, 105, 438–448. [Google Scholar] [CrossRef] [Scilit]
- Yu, S.N.; Huang, Y.K. Detection of Microcalcifications in Digital Mammograms using Combined Model-Based and Statistical Textural Features. Expert Syst. Appl. 2010, 37, 5461–5469. [Google Scholar] [CrossRef] [Scilit]
- Seneviratne, O.; Capuzzo, B.; Van Woensel, W. Explainability-Driven Quality Assessment for Rule-Based Systems. In Proceedings of the WWW ’25: Companion Proceedings of the ACM on Web Conference 2025, Sydney, NSW, Australia, 28 April–2 May 2025; pp. 2133–2140. [Google Scholar] [CrossRef] [Scilit]
- Elter, M.; Horsch, A. CADx of Mammographic Masses and Clustered Microcalcifications: A Review. Med. Phys. 2009, 36, 2052–2068. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Heath, M.; Bowyer, K.; Kopans, D.; Moore, R.; Kegelmeyer, W.P. The Digital Database for Screening Mammography. In Proceedings of the 5th International Workshop on Digital Mammography, Toronto, ON, Canada, 11–14 June 2000; pp. 212–218. [Google Scholar]
- Bajcsi, A.; Andreica, A.; Chira, C. Towards Feature Selection for Digital Mammogram Classification. Procedia Comput. Sci. 2021, 192, 632–641. [Google Scholar] [CrossRef] [Scilit]
- Boddu, A.S.; Jan, A. A Systematic Review of Machine Learning Algorithms for Breast Cancer Detection. Tissue Cell 2025, 95, 102929. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cortes, C.; Vapnik, V. Support-vector networks. Mach. Learn. 1995, 20, 273–297. [Google Scholar] [CrossRef] [Scilit]
- Khehra, B.S.; Pharwaha, A.P.S. Classification of Clustered Microcalcifications using MLFFBP-ANN and SVM. Egypt. Inform. J. 2016, 17, 11–20. [Google Scholar] [CrossRef] [Scilit]
- Zhang, X.; Gao, X. Twin Support Vector Machines and Subspace Learning Methods for Microcalcification Clusters Detection. Eng. Appl. Artif. Intell. 2012, 25, 1062–1072. [Google Scholar] [CrossRef] [Scilit]
- Mohamed, H.; Mabrouk, M.S.; Sharawy, A. Computer-Aided Detection System for Microcalcifications in Digital Mammograms. Comput. Methods Programs Biomed. 2014, 116, 226–235. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anitha, J.; Malathi, S. Machine Learning-Based Microcalcification Detection from Mammograms: Former Techniques and Challenges, Future Research Trends. Biomed. Eng. Appl. Basis Commun. 2025, 37, 2530003. [Google Scholar] [CrossRef] [Scilit]
- Diaz-Huerta, C.; Felipe-Riveron, E.; Montaño-Zetina, L. Quantitative Analysis of Morphological Techniques for Automatic Classification of Micro-Calcifications in Digitized Mammograms. Expert Syst. Appl. 2014, 41, 7361–7369. [Google Scholar] [CrossRef] [Scilit]
- Menon, S.P.; Naik, P.; Srikanteshwara, R. Breast Cancer Diagnosis Through Microcalcification. In Computational Intelligence and Modelling Techniques for Disease Detection in Mammogram Images; Hemanth, D.J., Ed.; Academic Press: Cambridge, MA, USA, 2024; pp. 151–175. [Google Scholar] [CrossRef] [Scilit]
- Savelli, B. Deep Learning for Computer-Aided Detection and Diagnosis of Clustered Microcalcifications on Digital Mammograms. Ph.D. Thesis, Università degli Studi di Cassino e del Lazio Meridionale, Cassino, Italy, 2020. [Google Scholar]
- Prinzi, F.; Orlando, A.; Gaglio, S.; Vitabile, S. Interpretable Radiomic Signature for Breast Microcalcification Detection and Classification. J. Imaging Inform. Med. 2024, 37, 1038–1053. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fanizzi, A.; Basile, T.M.A.; Losurdo, L.; Bellotti, R.; Bottigli, U.; Dentamaro, R.; Didonna, V.; Fausto, A.; Massafra, R.; Moschetta, M.; et al. A Machine Learning Approach on Multiscale Texture Analysis for Breast Microcalcification Diagnosis. BMC Bioinform. 2020, 21, 91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Suhail, Z.; Denton, E.R.E.; Zwiggelaar, R. Tree-based Modelling for the Classification of Mammographic Benign and Malignant Micro-calcification Clusters. Multimed. Tools Appl. 2018, 77, 6135–6148. [Google Scholar] [CrossRef] [Scilit]
- Aziz, S.A.A.; Ham, F.H.Y.; Ghafar, R.; Chia, L.C. Automatic Detection of Calcifications in Breast Cancer Diagnosis Based on Machine Learning Classifiers. In Proceedings of the 2024 IEEE 22nd Student Conference on Research and Development (SCOReD), Selangor, Malaysia, 19–20 December 2024; pp. 234–239. [Google Scholar] [CrossRef] [Scilit]
- Miron, M.; Moldovanu, S.; Ștefănescu, B.I.; Culea, M.; Pavel, S.M.; Culea-Florescu, A.L. A New Approach in Detectability of Microcalcifications in the Placenta during Pregnancy using Textural Features and K-Nearest Neighbors Algorithm. J. Imaging 2022, 8, 81. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lasztovicza, L.; Pataki, B.; Székely, N.; Tóth, N. Neural Network Based Microcalcification Detection in a Mammographic CAD System. Int. J. Comput. 2014, 3, 13–19. [Google Scholar] [CrossRef] [Scilit]
- Quintanilla-Domínguez, J.; Ruiz-Pinales, J.; Barrón-Adame, J.M.; Guzmán-Cabrera, R. Microcalcifications Detection using Image Processing. Comput. Sist. 2018, 22, 291–300. [Google Scholar] [CrossRef] [Scilit]
- Liang, H.; Li, J.; Wu, H.; Li, L.; Zhou, X.; Jiang, X. Mammographic Classification of Breast Cancer Microcalcifications through Extreme Gradient Boosting. Electronics 2022, 11, 2435. [Google Scholar] [CrossRef] [Scilit]
- Pesapane, F.; Trentin, C.; Ferrari, F.; Signorelli, G.; Tantrige, P.; Montesano, M.; Cicala, C.; Virgoli, R.; D’Acquisto, S.; Nicosia, L.; et al. Deep Learning Performance for Detection and Classification of Microcalcifications on Mammography. Eur. Radiol. Exp. 2023, 7, 69. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elumalai, S.; Rajendran, S.; Khalid, M. Breast Cancer Classification Based on Microcalcifications using Dual Branch Vision Transformer Fusion. Sci. Rep. 2026, 16, 4249. [Google Scholar] [CrossRef] [Scilit]
- Namsena, P.; Songsaeng, D.; Keatmanee, C.; Klabwong, S.; Kunapinun, A.; Soodchuen, S.; Tarathipayakul, T.; Tanasoontrarat, W.; Ekpanyapong, M.; Dailey, M.N. Diagnostic Performance of Artificial Intelligence in Interpreting Thyroid Nodules on Ultrasound Images: A Multicenter Retrospective Study. Quant. Imaging Med. Surg. 2024, 14, 3676–3694. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Şahin, E.; Arslan, N.N.; Özdemir, D. Unlocking the Black Box: An In-Depth Review on Interpretability, Explainability, and Reliability in Deep Learning. Neural Comput. Appl. 2025, 37, 859–965. [Google Scholar] [CrossRef] [Scilit]
- Kumar Singh, K.; Kumar, S.; Antonakakis, M.; Moirogiorgou, K.; Deep, A.; Kashyap, K.L.; Bajpai, M.K.; Zervakis, M. Deep Learning Capabilities for the Categorization of Microcalcification. Int. J. Environ. Res. Public Health 2022, 19, 2159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rehman, K.u.; Li, J.; Pei, Y.; Yasin, A.; Ali, S.; Mahmood, T. Computer Vision-Based Microcalcification Detection in Digital Mammograms using Fully Connected Depthwise Separable Convolutional Neural Network. Sensors 2021, 21, 4854. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shifa, N.; Saleh, M.; Akbari, Y.; Al Maadeed, S. A Review of Explainable AI Techniques and Their Evaluation in Mammography for Breast Cancer Screening. Clin. Imaging 2025, 123, 110492. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yurdusev, A.A.; Adem, K.; Hekim, M. Detection and Classification of Microcalcifications in Mammograms Images using Difference Filter and YOLOV4 Learning Model. Biomed. Signal Process. Control 2023, 80, 104360. [Google Scholar] [CrossRef] [Scilit]
- Liu, B.; Chen, H.; Zhu, T.; Ye, Z.; Cui, H.; Wang, K. Yolo-HLSAM: Adapting Foundation Segment Anything Model for Semi-Automatic Detection and Segmentation of Breast Cancer Microcalcification Clusters. Biomed. Signal Process. Control 2026, 111, 108300. [Google Scholar] [CrossRef] [Scilit]
- Cai, Z.; Zhou, K.; Liao, Z. A Systematic Review of YOLO-Based Object Detection in Medical Imaging: Advances, Challenges, and Future Directions. Comput. Mater. Contin. 2025, 85, 2255–2303. [Google Scholar] [CrossRef] [Scilit]
- Kang, D.; Gweon, H.M.; Eun, N.L.; Youk, J.H.; Kim, J.A.; Son, E.J. A Convolutional Deep Learning Model for Improving Mammographic Breast-Microcalcification Diagnosis. Sci. Rep. 2021, 11, 23925. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Teoh, J.R.; Hasikin, K.; Lai, K.W.; Wu, X.; Li, C. Enhancing Early Breast Cancer Diagnosis through Automated Microcalcification Detection using an Optimized Ensemble Deep Learning Framework. PeerJ Comput. Sci. 2024, 10, e2082. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Luna Lozoya, R.S.; Ochoa Domínguez, H.d.J.; Sossa Azuela, J.H.; Cruz Sánchez, V.G.; Vergara Villegas, O.O.; Núñez Barragán, K. Cross-Domain Transfer Learning Architecture for Microcalcification Cluster Detection using the MEXBreast Multiresolution Mammography Dataset. Mathematics 2025, 13, 2422. [Google Scholar] [CrossRef] [Scilit]
- Wang, K.; Ye, Z.; Xie, X.; Cui, H.; Chen, T.; Liu, B. MLN-net: A Multi-Source Medical Image Segmentation Method for Clustered Microcalcifications using Multiple Layer Normalization. Knowl.-Based Syst. 2024, 283, 111127. [Google Scholar] [CrossRef] [Scilit]
- Honjo, T.; Ueda, D.; Katayama, Y.; Shimazaki, A.; Jogo, A.; Kageyama, K.; Murai, K.; Tatekawa, H.; Fukumoto, S.; Yamamoto, A.; et al. Visual and Quantitative Evaluation of Microcalcifications in Mammograms with Deep Learning-Based Super-Resolution. Eur. J. Radiol. 2022, 154, 110433. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hsu, P.Y.; Xu, J.L.; Chen, L.L.; Chen, M.Y. Using Deep Learning to Construct Microcalcification Clusters in a Mammography Prediction Model. Innov. Emerg. Technol. 2025, 12, 2550030. [Google Scholar] [CrossRef] [Scilit]
- Sarvestani, Z.M.; Jamali, J.; Taghizadeh, M.; Dindarloo, M.H.F. A Novel Machine Learning Approach on Texture Analysis for Automatic Breast Microcalcification Diagnosis Classification of Mammogram Images. J. Cancer Res. Clin. Oncol. 2023, 149, 6151–6170. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.; Nishikawa, R.M.; Yang, Y. Global Detection Approach for Clustered Microcalcifications in Mammograms using a Deep Learning Network. J. Med. Imaging 2017, 4, 024501. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cai, H.; Huang, Q.; Rong, W.; Song, Y.; Li, J.; Wang, J.; Chen, J.; Li, L. Breast Microcalcification Diagnosis using Deep Convolutional Neural Network from Digital Mammograms. Comput. Math. Methods Med. 2019, 2019, 2717454. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sharma, S.; Singh, Y.; Choudhury, T. Advanced Deep Learning Architectures for Enhanced Mammography Classification: A Comparative Study of CNNs and ViT. Discov. Artif. Intell. 2025, 5, 187. [Google Scholar] [CrossRef] [Scilit]
- Gerbasi, A.; Clementi, G.; Corsi, F.; Albasini, S.; Malovini, A.; Quaglini, S.; Bellazzi, R. DeepMiCa: Automatic Segmentation and Classification of Breast Microcalcifications from Mammograms. Comput. Methods Programs Biomed. 2023, 235, 107483. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, X.; Wang, Z. A Microcalcification Cluster Detection Method Based on Deep Learning and Multi-Scale Feature Fusion. J. Supercomput. 2019, 75, 5808–5830. [Google Scholar] [CrossRef] [Scilit]
- Joseph, B.; Ramachandran, B.; Muthukrishnan, P. Intelligent Detection and Classification of Microcalcification in Compressed Mammogram Image. Image Anal. Stereol. 2015, 34, 183–198. [Google Scholar] [CrossRef] [Scilit]
- Singla, C.; Bhardwaj, R.; Shelke, N.; Singh, G. Data Augmentation: Synthetic Image Generation for Medical Images using Vector Quantized Variational Autoencoders. In Proceedings of the 2025 3rd International Conference on Disruptive Technologies (ICDT), Greater Noida, India, 7–8 March 2025; pp. 1502–1507. [Google Scholar] [CrossRef] [Scilit]
- Xu, W.; Deng, S.; Mao, G.; Wang, N.; Huang, Y.; Zhang, C.; Sa, G.; Wu, S.; An, Y. Differentiation of Suspicious Microcalcifications using Deep Learning: DCIS or IDC. Acad. Radiol. 2025, 32, 6612–6622. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shia, W.C. Deep Learning-Based Classification of Benign and Malignant Breast Microcalcifications in Mammography. Sci. Rep. 2025, 15, 42768. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rehman, K.U.; Li, J.; Yasin, A.; Bilal, A.; Basheer, S.; Ullah, I.; Jabbar, M.K.; Tian, Y. A Feature Fusion Attention-Based Deep Learning Algorithm for Mammographic Architectural Distortion Classification. IEEE J. Biomed. Health Inform. 2026, 30, 2793–2804. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Loizidou, K.; Skouroumouni, G.; Nikolaou, C.; Pitris, C. An Automated Breast Micro-Calcification Detection and Classification Technique using Temporal Subtraction of Mammo-grams. IEEE Access 2020, 8, 52785–52795. [Google Scholar] [CrossRef] [Scilit]
- Luna Lozoya, R.S.; Núñez Barragán, K.; Ochoa Domínguez, H.d.J.; Sossa Azuela, J.H.; Cruz Sánchez, V.G.; Vergara Villegas, O.O. Mexican Dataset of Digital Mammograms (MEXBreast) with Suspicious Clusters of Microcalcifications. Data Brief. 2025, 60, 111587. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, J.; Yang, X.; Cai, H.; Tan, W.; Jin, C.; Li, L. Discrimination of Breast Cancer with Microcalcifications on Mammography by Deep Learning. Sci. Rep. 2016, 6, 27327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mahmood, T.; Li, J.; Pei, Y.; Akhtar, F.; Imran, A.; Yaqub, M. An Automatic Detection and Localization of Mammographic Microcalcifications ROI with Multi-Scale Features using the Radiomics Analysis Approach. Cancers 2021, 13, 5916. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Leong, Y.S.; Hasikin, K.; Lai, K.W.; Mohd Zain, N.; Azizan, M.M. Microcalcification Discrimination in Mammography using Deep Convolutional Neural Network: Towards Rapid and Early Breast Cancer Diagnosis. Front. Public Health 2022, 10, 875305. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moreira, I.C.; Amaral, I.; Domingues, I.; Cardoso, A.; Cardoso, M.J.; Cardoso, J.S. INbreast: Toward a Full-Field Digital Mammographic Database. Acad. Radiol. 2012, 19, 236–248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guevara López, M.A.; González de Posada, N.; Moura, D.C.; Ramos Pollán, R.; Franco Valiente, J.M.; Suárez Ortega, C.; del Solar, M.R.; Díaz Herrero, G.; Pereira Ramos, I.M.A.; Pinheiro Loureiro, J.; et al. BCDR: A Breast Cancer Digital Repository. In Proceedings of the 15th International Conference on Experimental Mechanics (ICEM15), Porto, Portugal, 22–27 July 2012; pp. 1065–1066. [Google Scholar]
- Sawyer-Lee, R.; Gimenez, F.; Hoogi, A.; Rubin, D. Curated Breast Imaging Subset of Digital Database for Screening Mammography (CBIS-DDSM) [Data Set]; The Cancer Imaging Archive: Little Rock, AR, USA, 2016. [Google Scholar] [CrossRef] [Scilit]
- Ben Ammar, M.; Ayachi, F.L.; Cardoso de Paiva, A.; Ksantini, R.; Mahjoubi, H. Harnessing Deep Learning for Early Breast Cancer Diagnosis: A Review of Datasets, Methods, Challenges, and Future Directions. Int. J. Comput. Digit. Syst. 2024, 16, 1643–1661. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ahmed, S.F.; Alam, M.S.B.; Hassan, M.; Rozbu, M.R.; Ishtiak, T.; Rafa, N.; Mofijur, M.; Shawkat Ali, A.B.M.; Gandomi, A.H. Deep Learning Modelling Techniques: Current Progress, Applications, Advantages, and Challenges. Artif. Intell. Rev. 2023, 56, 13521–13617. [Google Scholar] [CrossRef] [Scilit]
- Chan, H.P.; Samala, R.K.; Hadjiiski, L.M.; Zhou, C. Deep Learning in Medical Image Analysis. In Deep Learning in Medical Image Analysis: Challenges and Applications; Advances in Experimental Medicine and Biology; Lee, G., Fujita, H., Eds.; Springer: Cham, Switzerland, 2020; Volume 1213, pp. 3–21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gao, Y.; Lin, J.; Zhou, Y.; Lin, R. The Application of Traditional Machine Learning and Deep Learning Techniques in Mammography: A Review. Front. Oncol. 2023, 13, 1213045. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kumar, A.; Kumar, T.A.; Das, P.; Sharma, C.; Dubey, A.K. (Eds.) Explainable Artificial Intelligence in the Healthcare Industry; John Wiley and Sons: Hoboken, NJ, USA, 2025. [Google Scholar] [CrossRef] [Scilit]
- Mikulić, M.; Vičević, D.; Nagy, E.; Napravnik, M.; Štajduhar, I.; Tschauner, S.; Hržić, F. Balancing Performance and Interpretability in Medical Image Analysis: Case Study of Osteopenia. J. Imaging Inform. Med. 2025, 38, 177–190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- J, B.; R, J.; Richard, T.; Chowdhury, R.; Kumar, P.; Radhika, K. Evaluating Generative Adversarial Networks Performance in Image Synthesis with Graphical Analysis of Loss Functions and Quality Metrics. In Proceedings of the 2024 International Conference on Integrated Intelligence and Communication Systems (ICIICS), Kalaburagi, India, 22–23 November 2024; pp. 1–8. [Google Scholar] [CrossRef] [Scilit]
- Abdulqader, M.M.; Abdulazeez, A.M. A Comparative Study of Generative Adversarial Networks in Medical Image Processing. Eng 2025, 6, 291. [Google Scholar] [CrossRef] [Scilit]
- Lee, J.; Mustafaev, T.; Nishikawa, R.M. Impact of GAN Artifacts for Simulating Mammograms on Identifying Mammographically Occult Cancer. J. Med. Imaging 2023, 10, 054503. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schiavo, J.H. PROSPERO: An International Register of Systematic Review Protocols. Med. Ref. Serv. Q. 2019, 38, 171–180. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bobowicz, M.; Koh, D.M.; Penzkofer, T.; Regge, D.; Riklund, K.; Martinez-Girones, P.M.; Fütterer, J.; Lekadir, K.; Tsakou, G.; Marti-Bonmati, L. The Clinical Considerations for Trustworthy AI in Oncologic Imaging. In Trustworthy AI in Cancer Imaging Research; Springer Nature: Cham, Switzerland, 2025; pp. 23–52. [Google Scholar] [CrossRef] [Scilit]
- Loizidou, K.; Skouroumouni, G.; Nikolaou, C.; Pitris, C. Automatic Breast Mass Segmentation and Classification using Subtraction of Temporally Sequential Digital Mammograms. IEEE J. Transl. Eng. Health Med. 2022, 10, 1801111. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, Z.; Arefan, D.; Zuley, M.; Hao, D.; Sumkin, J.; Wu, S. Knowledge-Guided Multi-Task Learning for Breast Cancer Diagnosis using Longitudinal Mammogram Images. In Proceedings of the 2024 IEEE International Symposium on Biomedical Imaging (ISBI), Athens, Greece, 27–30 May 2024; pp. 1–5. [Google Scholar] [CrossRef] [Scilit]
- Halling-Brown, M.D.; Warren, L.M.; Ward, D.; Lewis, E.; Mackenzie, A.; Wallis, M.G.; Wilkinson, L.S.; Given-Wilson, R.M.; McAvinchey, R.; Young, K.C. OPTIMAM Mammography Image Database: A Large-Scale Resource of Mammography Images and Clinical Data. Radiol. Artif. Intell. 2021, 3, e200103. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jeong, J.; Vey, B.L.; Bhimireddy, A.; Kim, T.; Santos, T.; Correa, R.; Dutt, R.; Mosunjac, M.; Oprea-Ilies, G.; Smith, G.; et al. The EMory BrEast Imaging Dataset (EMBED): A Racially Diverse, Granular Dataset of 3.4 Million Screening and Diagnostic Mammographic Images. Radiol. Artif. Intell. 2023, 5, e220047. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nikolenko, S.I. Synthetic Data for Deep Learning; Springer: Cham, Switzerland, 2021. [Google Scholar] [CrossRef] [Scilit]
- Kowalczuk, Z.; Glinko, J. Training of Deep Learning Models using Synthetic Datasets. In Intelligent and Safe Computer Systems in Control and Diagnostics; Springer: Cham, Switzerland, 2023; pp. 141–152. [Google Scholar] [CrossRef] [Scilit]
- Shahid, M.S.; Imran, A. Breast Cancer Detection using Deep Learning Techniques: Challenges and Future Directions. Multimed. Tools Appl. 2025, 84, 3257–3304. [Google Scholar] [CrossRef] [Scilit]
- Zou, L.; Sun, J.; Li, J.; Tang, H.; Zhou, G.; Coatrieux, G.; Coatrieux, J.L.; Chen, Y.; Jiang, Y. A Multi-group Similarity-Decoding-Based Method for Deep Model Ensembling Applied in the Microcalcification Classification on Digital Mammograms. Biomed. Signal Process. Control 2024, 91, 105896. [Google Scholar] [CrossRef] [Scilit]
- Nagashruthi, M.K.; Hemanth, K.S. Artificial Intelligence and Machine Learning in Clinical Care: Revolutionizing Decision Support. In Innovation in Healthtech: A Roadmap for Empowering Healthcare; CRC Press: Boca Raton, FL, USA, 2025; pp. 95–116. [Google Scholar] [CrossRef] [Scilit]
- Ahmadpour, S.S.; Avval, D.B.; Darbandi, M.; Navimipour, N.J.; Ain, N.U.; Kassa, S. A New Quantum-Enhanced Approach to AI-Driven Medical Imaging System. Clust. Comput. 2025, 28, 213. [Google Scholar] [CrossRef] [Scilit]
- Abdel-Khalek, S. Leveraging Quantum Neural Networks with Deep Learning Based Edge Detection Model for Breast Cancer Screening using Digital Mammograms. J. Intell. Syst. Internet Things 2025, 16, 68–81. [Google Scholar] [CrossRef] [Scilit]
- Tariq Jamal, A.; Ben Ishak, A.; Abdel-Khalek, S. Tumor Edge Detection in Mammography Images using Quantum and Machine Learning Approaches. Neural Comput. Appl. 2021, 33, 7773–7784. [Google Scholar] [CrossRef] [Scilit]
- Golchha, R.; Verma, G.K. Leveraging Quantum Computing for Synthetic Image Generation and Recognition with Generative Adversarial Networks and Convolutional Neural Networks. Int. J. Inf. Technol. 2024, 16, 3149–3162. [Google Scholar] [CrossRef] [Scilit]
- Stelzer, P.D.; Steding, O.; Raudner, M.W.; Euller, G.; Clauser, P.; Baltzer, P.A.T. Combined Texture Analysis and Machine Learning in Suspicious Calcifications Detected by Mammography: Potential to Avoid Unnecessary Stereotactical Biopsies. Eur. J. Radiol. 2020, 132, 109309. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oliver, A.; Torrent, A.; Lladó, X.; Tortajada, M.; Tortajada, L.; Sentís, M.; Freixenet, J.; Zwiggelaar, R. Automatic Microcalcification and Cluster Detection for Digital and Digitised Mammograms. Knowl.-Based Syst. 2012, 28, 68–75. [Google Scholar] [CrossRef] [Scilit]
- Quintanilla-Dominguez, J.; Cortina-Januchs, M.G.; Ojeda-Magaña, B.; Jevtić, A.; Vega-Corona, A.; Andina, D. Microcalcification Detection Applying Artificial Neural Networks and Mathematical Morphology in Digital Mammograms. In Proceedings of the 2010 World Automation Congress, Kobe, Japan, 19–23 September 2010; pp. 1–6. [Google Scholar]
- Brahimetaj, R.; Willekens, I.; Massart, A.; Forsyth, R.; Cornelis, J.; De Mey, J.; Jansen, B. Improved Automated Early Detection of Breast Cancer Based on High Resolution 3D Micro-CT Microcalcification Images. BMC Cancer 2022, 22, 162. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schönenberger, C.; Hejduk, P.; Ciritsis, A.; Marcon, M.; Rossi, C.; Boss, A. Classification of Mammographic Breast Microcalcifications using a Deep Convolutional Neural Network: A BI-RADS-Based Approach. Investig. Radiol. 2021, 56, 224–231. [Google Scholar] [CrossRef] [Scilit]
- Michiel, K.; Kersten, P.; Mads, N.; Ng, A.Y.; Diao, P.; Igel, C.; Vachon, C.M.; Holland, K.; Winkel, R.R.; Karssemeijer, N.; et al. Unsupervised Deep Learning Applied to Breast Density Segmentation and Mammographic Risk Scoring. IEEE Trans. Med. Imaging 2016, 35, 1322–1331. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malarvizhi, A.; Andiappan, N. Implementation of Improved U-Net and Optimized XGBoost-SVM Classifier for Early Detection of Masses and Microcalcifications in Breast. Front. Biomed. Technol. 2024, 11, 344–360. [Google Scholar] [CrossRef] [Scilit]
- Suzuki, K. Overview of Deep Learning in Medical Imaging. Radiol. Phys. Technol. 2017, 10, 257–273. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oyelade, O.N.; Ezugwu, A.E.; Almutairi, M.S.; Saha, A.K.; Abualigah, L.; Chiroma, H. A Generative Adversarial Network for Synthetization of Regions of Interest Based on Digital Mammograms. Sci. Rep. 2022, 12, 6166. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joseph, A.J.; Dwivedi, P.; Joseph, J.; Francis, S.; Pournami, P.N.; Jayaraj, P.B.; Shamsu, A.V.; Sankaran, P. Prior-Guided Generative Adversarial Network for Mammogram Synthesis. Biomed. Signal Process. Control 2024, 87, 105456. [Google Scholar] [CrossRef] [Scilit]
- Shia, W.C.; Ku, T.H. Enhancing Microcalcification Detection in Mammography with YOLO-v8 Performance and Clinical Implications. Diagnostics 2024, 14, 2875. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Songyang, Y.; Ling, G. A CAD System for the Automatic Detection of Clustered Microcalcifications in Digitized Mammogram Films. IEEE Trans. Med. Imaging 2000, 19, 115–126. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mabrouk, M.S.; Afify, H.M.; Marzouk, S.Y. Fully Automated Computer-Aided Diagnosis System for Microcalcifications Cancer Based on Improved Mammographic Image Techniques. Ain Shams Eng. J. 2019, 10, 517–527. [Google Scholar] [CrossRef] [Scilit]
- Shiri, K.M.; Giti, M.; Akhaee, M.A.; Ameri, A. Microcalcification Detection in Mammograms using Deep Learning. IJ Radiol. 2022, 19, e120758. [Google Scholar] [CrossRef] [Scilit]


| SPICE Element | Input | Scenario |
|---|---|---|
| S—Setting | Clinical context and primary modality | Early breast cancer detection via mammography. |
| P—Perspective | Research perspective | Researchers and developers. |
| I—Intervention | Deep learning approaches | Development and application of DL models, particularly Convolutional Neural Networks (CNN). |
| C—Comparison | Conventional approaches | Traditional ML methods and rule-based systems. |
| E—Evaluation | Performance metrics | Sensitivity, specificity, generalizability, and the Area Under the Curve (AUC). |
| SPICE Element | Input | Scenario |
|---|---|---|
| S—Setting | Transition from research to clinical practice | Clinical implementation of AI for the detection of MCs and MCCs. |
| P—Perspective | Healthcare stakeholders | Radiologists, hospital administrators, and workflow specialists concerned with clinical integration and usability. |
| I—Intervention | Explainability in DL systems | Integration of explainable AI (XAI) techniques into deep learning models. |
| C—Comparison | Standard DL approaches | Black-box deep learning models versus XAI-enhanced models. |
| E—Evaluation | Human and operational outcomes | Radiologist trust, diagnostic confidence, workflow efficiency, and clinical adoption. |
| SPICE Element | Input | Scenario |
|---|---|---|
| S—Setting | Data-centric challenges in AI | Medical imaging contexts with limited, imbalanced, or privacy-constrained datasets. |
| P—Perspective | Technical perspective | Data scientists and ML researchers focusing on model robustness and generalization. |
| I—Intervention | Synthetic data generation | Use of synthetic data to augment training datasets. |
| C—Comparison | Training strategies | Models trained on real data versus hybrid datasets (real + synthetic). |
| E—Evaluation | Model performance outcomes | Performance, generalizability across different clinical settings, and reduction in dataset bias. |
| Dimension | Qureshi et al. [13] | Bashir and Bhosle [14] | Añez et al. [15] | van Leeuwen et al. [16] | Present Review |
|---|---|---|---|---|---|
| Scope | ML, DL | MC seg. | Pipeline | Clinical | DL vs. ML + XAI + Synthetic |
| AI focus | Broad | MC | Pipeline | None | MC detection |
| PRISMA | Yes | No | Yes | Yes | Yes |
| SPICE/RQs | No | No | No | No | Yes |
| XAI | None | None | Implemented | None | Evidence gap analysis |
| Synthetic data | None | None | None | None | Yes |
| Risk of bias | – | – | PROBAST | QUIPS | Domain-specific |
| N studies integration | 150+ | – | – | Meta | 72 |
| Longitudinal studies | No | No | No | No | Gap identified |
| Component | Details |
|---|---|
| Objective | To identify studies on visual inspection, rule-based systems, and ML/DL methods for MC detection in digital mammography for early breast cancer detection. |
| Databases | Web of Science, Scopus, PubMed, IEEE Xplore, ScienceDirect, SpringerLink, and Google Scholar |
| Timeframe | January 2000 to January 2026 |
| Search Concepts |
|
| Search Terms |
|
| Boolean Logic | (mammogra* OR mammogram* OR “breast imaging”) AND (microcalcif* OR calcif* OR MC OR MCC OR “calcification cluster*”) AND (“visual inspection” OR “rule-based” OR “machine learning” OR “deep learning” OR “artificial intelligence” OR AI OR “computer-aided detection” OR CNN OR SVM OR “random forest”) AND (detect* OR classif* OR diagnos* OR segment*) AND (“explainable AI” OR “XAI” OR “interpretability” OR “synthetic data” OR “data augmentation”) |
| Inclusion Criteria |
|
| Exclusion Criteria |
|
| Additional Search | Manual screening of reference lists (backward snowballing) |
| Component | Details |
|---|---|
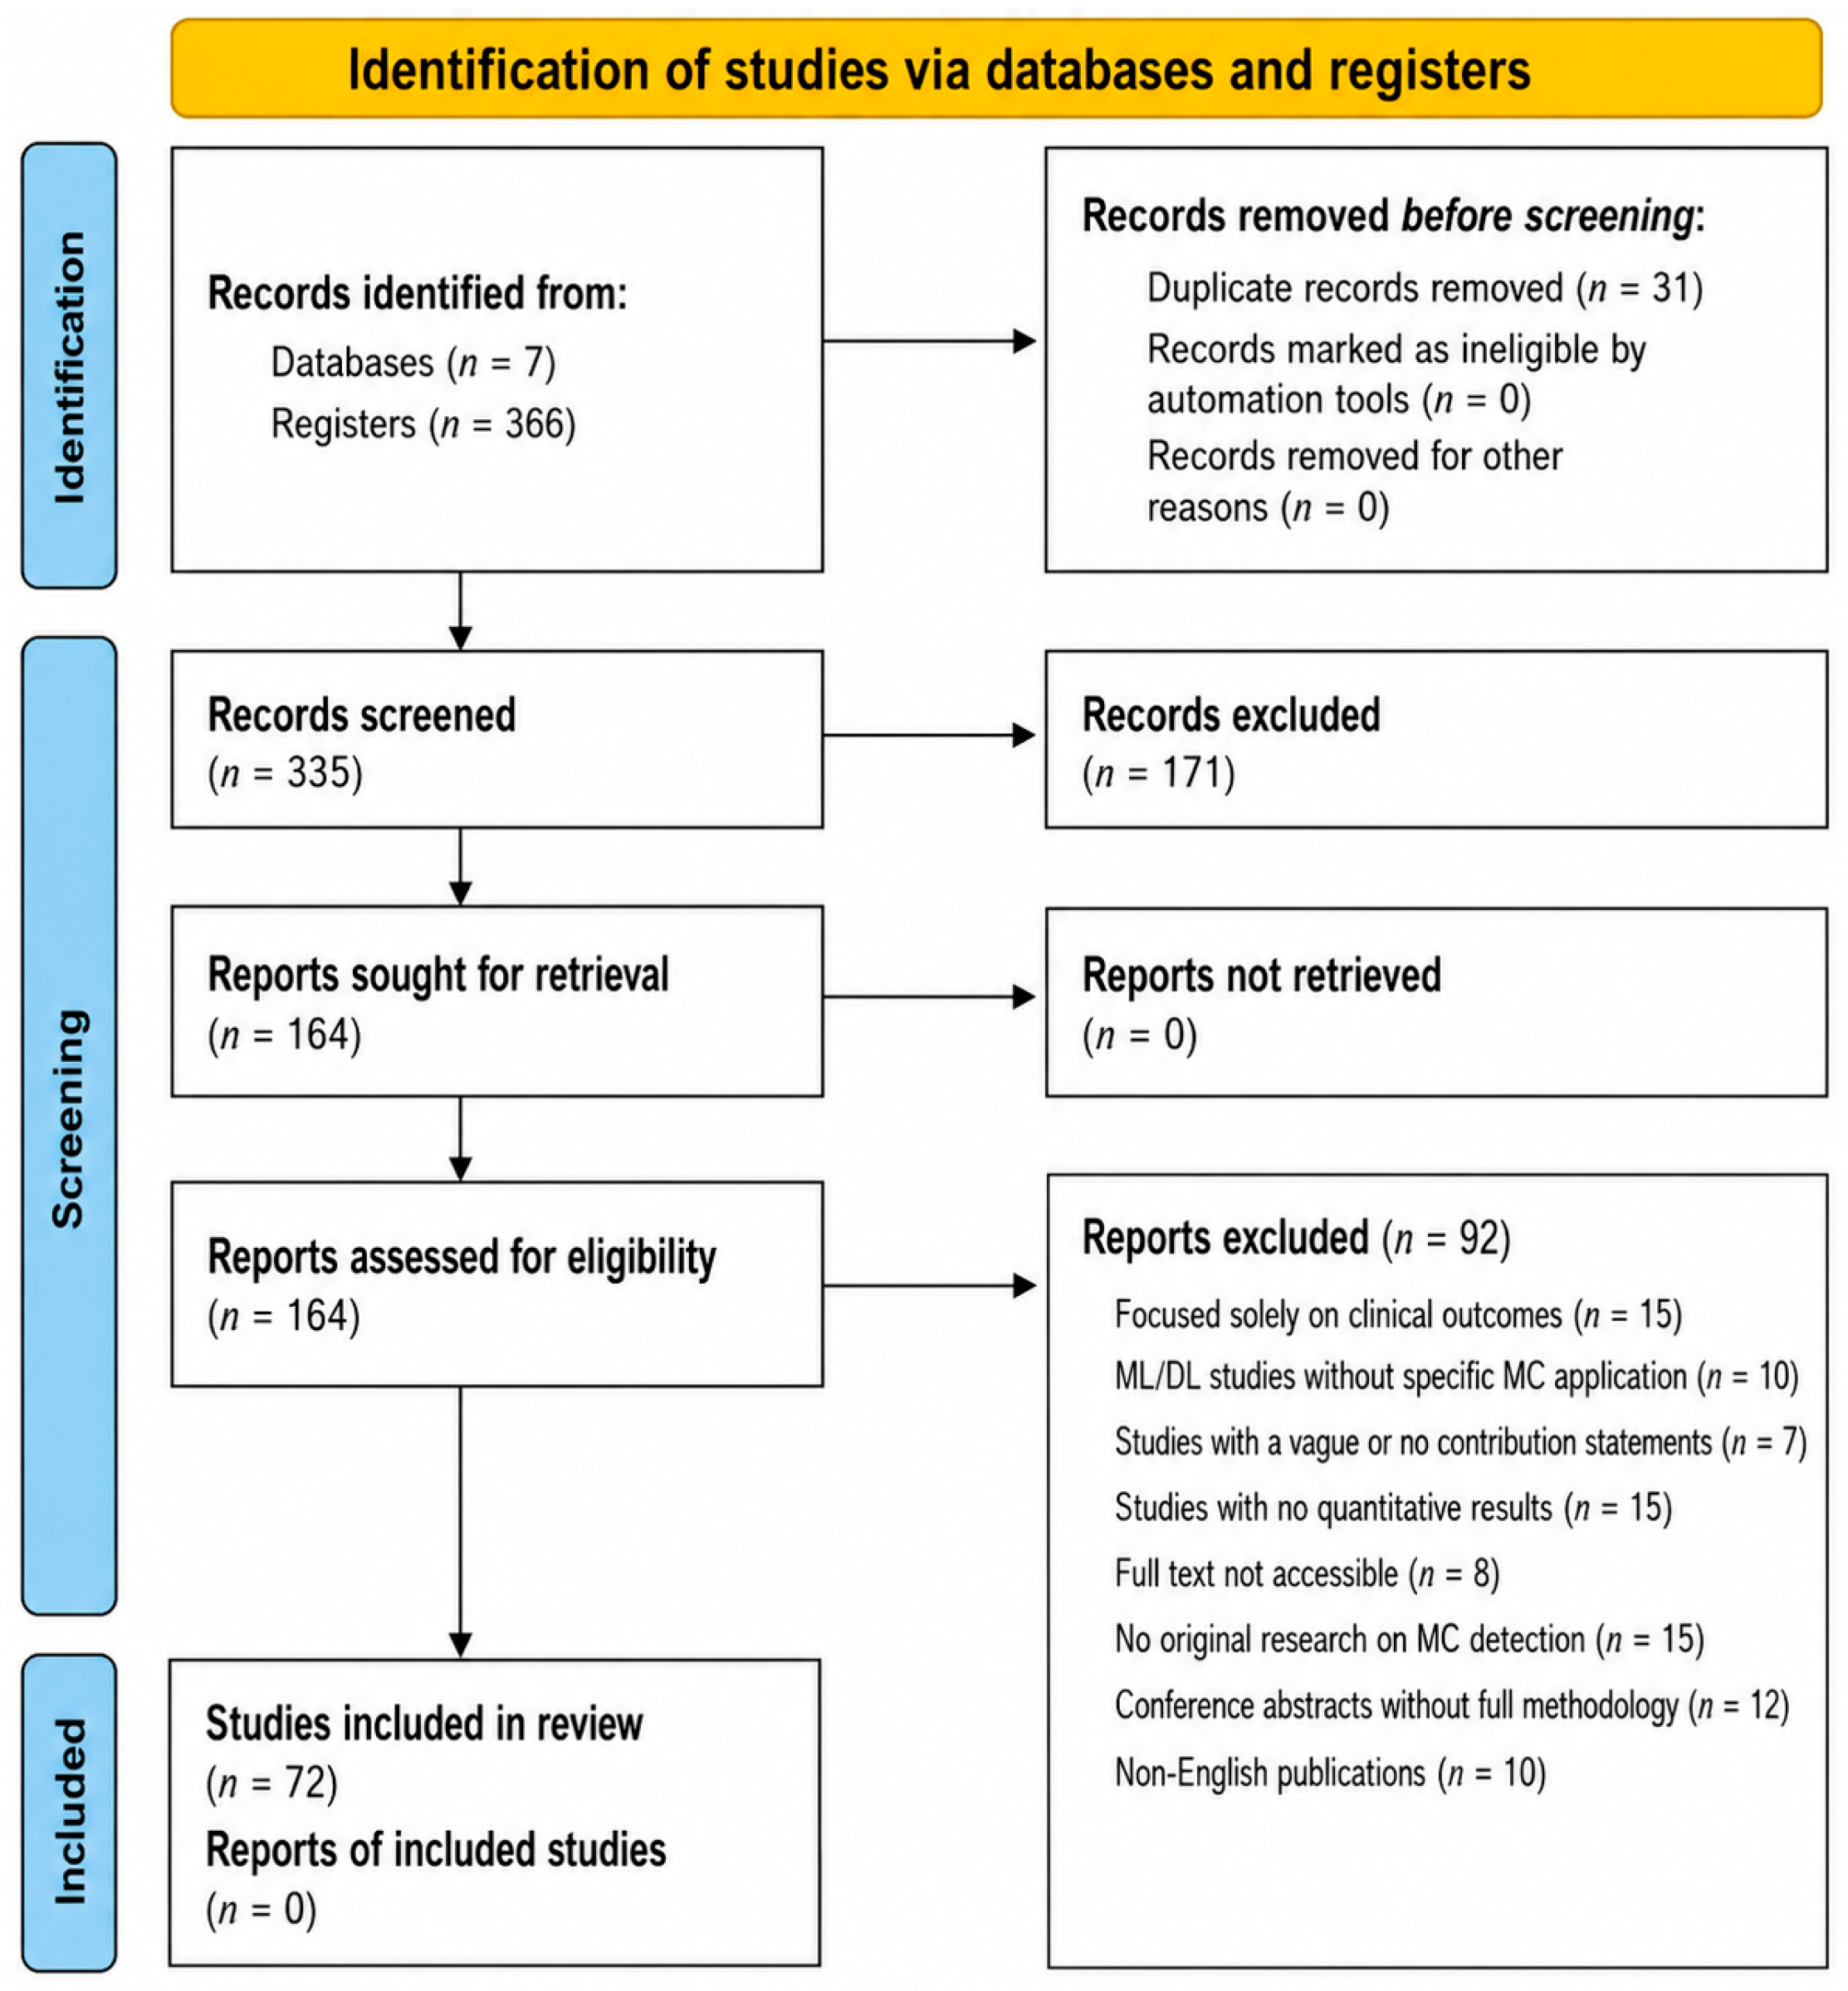
| Identification | 366 records identified; 31 duplicates records removed prior to screening |
| Screening Phase 1: Title/Abstract |
|
| Screening Phase 2: Full-Text Assessment |
|
| Final Included Studies |
|
| Contextual References |
|
| Component | Description |
|---|---|
| Contextual documents | 9 |
| Sources | Selected primary and foundational studies from the 72 included articles, along with relevant background papers from the 92 articles excluded during the full-text review. |
| Purpose | Provide clinical and methodological context; support the Section 1, the Factors affecting the MC detection sections, and frame the research problem. Provide definitions, ML/DL mathematics, models, advancements in the classic ML. |
| Method | Paradigm | Feature Dependency | Strengths | Key Limitations |
|---|---|---|---|---|
| Visual Inspection | Human expert analysis. | No explicit feature extraction. | Integrates clinical context; adaptable to complex cases. | Subjective; inter-observer variability; fatigue-related errors. |
| Rule-based Systems | Deterministic/heuristic. | Handcrafted image features. | Interpretable; clinically trans-parent workflow. | Poor generalization; limited adapt-ability to imaging variability. |
| SVM | Classical machine learning. | Strong dependence on engineered features. | Effective in high-dimensional separable spaces. | Sensitive to noise; limited modeling of complex morphology. |
| Random Forest | Ensemble learning. | Moderate feature engineering required. | High accuracy; reduced over-fitting. | Limited interpretability; weaker performance on complex patterns. |
| k-NN | Instance-based learning. | Distance-based feature space dependency. | Simple; effective with well-designed descriptors. | High computational cost; sensitive to dimensionality and irrelevant features. |
| ANNs | Shallow neural learning. | Learned features (limited depth). | Improved adaptability over classical ML. | Overfitting risk; limited robust-ness across imaging domains. |
| Decision Trees | Rule-based learning. | Moderate feature dependence. | Highly interpretable decision paths. | Overfitting; limited scalability to complex imaging data. |
| Naive Bayes | Probabilistic learning. | Strong independence assumption. | Fast; computationally efficient. | Poor modeling of feature correlations in imaging data. |
| XGBoost | Boosted ensemble learning. | Feature-engineered or hybrid features. | High predictive performance; strong non-linear modeling. | Reduced interpretability; sensitive to dataset bias and feature quality. |
| Deep Learning | Representation learning (CNN-based). | Minimal manual feature engineering. | State-of-the-art accuracy; automatic hierarchical feature extraction; strong performance on MC/MCC patterns. | Requires large annotated datasets; domain shift sensitivity; limited interpretability; false positives in dense tissue. |
| Dataset | Size/Patients | Imaging Type | Limitations |
|---|---|---|---|
| MIAS [34] | 322 images/161 patients | SFM (digitized) | Very small scale; outdated screen-film modality; limited annotation precision (approximate lesion centers only); not representative of modern FFDM data. |
| INbreast [101] | 410 images/115 patients | FFDM (70 μm) | Limited dataset size reduces generalization ability; class imbalance; single-center acquisition limits domain diversity. |
| BCDR [102] | Multiple sub-sets | SFM and FFDM | Moderate annotation granularity; variability between film and digital subsets; limited standardization compared to newer datasets. |
| DDSM [50] | ∼2620 cases | SFM (digitized) | Old imaging modality (screen-film); digitization noise; inconsistent annotation quality; requires extensive preprocessing for DL. |
| CBIS-DDSM [103] | Curated subset of DDSM | SFM (digitized) | Still inherits limitations of DDSM; lacks FFDM characteristics; reduced variability due to preprocessing pipeline. |
| MEXBreast [97] | 620 images | Multi-resolution FFDM (50, 70, 100 µm) | Limited public benchmarking adoption; relatively small scale compared to DDSM. |
| Metric | Rule-Based | ML-Based | DL-Based |
|---|---|---|---|
| Sensitivity | 96.5% [46] | 94.4% [55] | 100% [29] |
| Accuracy | 90.16% [55] | 97.31% [62] | 99.71% [11] |
| AUC | 0.9677 [55] | 0.9816 [62] | 0.998 [94] |
| Limitation | Description |
|---|---|
| GAN-Based Arti-facts | Checkerboard artifacts with a high incidence (39–46%). Breast boundary artifacts show the highest incidence (34–53%). Other issues include abnormal nipple-areola appearance and black spots around calcifications and MCCs, particularly in cancer cases (16%). |
| GAN General Limitations | Artifact incidence (69–78%) in normal tissue. Multiple artifacts may appear simultaneously in the same simulated mammogram (38%). This increases the risk of false positives during detection. |
| Data Requirements | Need for large training datasets. Risk of overfitting when data is limited. |
| Interpretability | Limited interpretability of GAN-generated outputs restricts clinical applicability. |
| Three-dimensional Model Limitations | Extensive parameter tuning to model realistically small structures due to voxel size constraints. These methods also require accurate characterization for each imaging system. |
| Hybrid Simulation Framework Limitations | Lesion integration with breast textures is challenging and may incorrectly focus on pectoral muscle or skin folds. Accurate breast masks are required, and generating correlated CC and MLO views remains difficult. |
| Validation and Assessment Limitations | Validation studies are commonly restricted to a limited number of radiologists and datasets. Multi-vendorvalidationisrare, establishingreliablegroundtruthischallenging, andverification using magnification images is often impractical. Validation outcomes may also depend on the observer. |
| General/Other | Some methods are currently limited to simulating single MCs instead of full clusters. |
| Author, Year | Design | Images | Method | Dataset(s) | Key Findings/Metrics |
|---|---|---|---|---|---|
| Yu (2010) [47] | MCs detection | 20 | Rule + ML-based | MIAS | Sensitivity: 94% (FP: 1.0/img) or 90% (FP: 0.65/img). Model-based and statistical textural features improve detection. |
| Halkiotis (2007) [42] | MCCs detection | 53 | ANN + Morphology | MIAS | Sensitivity: 94.7%, FP: 0.27/img. Topographic features improve CAD. |
| Papadopoulos (2008) [37] | MCCs detection | 26 | Rule-based | MIAS + Private | AZ = 0.932. WT enhancement and LRM improve CAD. |
| Malar et al. (2012) [45] | MCs detection/classif. | 400 | Extreme Learning Machine | DoD BCRP | Accuracy: 94%. Wavelet features outperform other texture features. |
| Mohanalin (2014) [46] | MCs detection | 247 | WT + Thresholding | MIAS + UCSF | FROC: Sensitivity 96.5%, FP: 0.36/img. Entropy-based thresholding improves accuracy. |
| Ge (2007) [44] | MCCs detection | 192 | Rule + Classifier + CNN | Private | FFDM sensitivity: 70%, 80%, 90% (FP: 0.07, 0.16, 0.63/img). SFM FP: 0.15, 0.38, 2.02/img. FFDM outperforms SFM. |
| Ciecholewski (2017) [36] | MCs detect. + seg. | 200 | Rule-based | MIAS + DDSM | Similarity: 80.5%, Overlap: 75.7%, Extra: 19.8%. Runtime: 0.83 s/ROI. Fast automated method. |
| Alasadi (2017) [35] | MCs detection | 66 | Rule-based | MIAS | Sensitivity: 93.1%, FP: 10%. Image enhancement improves detection but variability remains. |
| Linguraru et al. (2006) [43] | MCs detection | 83 | Biologically inspired | DDSM | Sensitivity: 100%, FP: ∼2/img. Method is robust and reproducible. |
| Bajcsi (2021) [51] | Early breast cancer detection | 322 | k-means, GLRLM, PCA, GA, DT, RF | MIAS | GLRLM features (45°, 90°) best. PCA outperformed GA. RF achieved 100% training and 70% test accuracy. |
| Zhang (2012) [55] | MCCs detection | 267 | TWSVM + subspace learning | DDSM | Accuracy: 90.16%, Sensitivity: 94.42%, FPR: 8.32% ± 1.04, AUC: 0.9677. |
| Khehra (2016) [54] | MCCs classification | 200 | MLFFBP-ANN, SMO-SVM | Private | SMO-SVM best with 90.16% accuracy. Linear SVM effective for MCC classification. |
| Aziz (2024) [64] | Calcifications classification | 30 | RF, SVM, k-NN | Private | RF achieved ∼97% accuracy, outperforming k-NN. Further improvements needed for clinical-grade performance. |
| Miron (2022) [65] | Placental MCs detection | 150 | k-NN, SVM | Private (placenta) | k-NN: 84.01% accuracy; SVM: 76%. Results improve detectability of placental MCs in clinical data. |
| Menon (2024) [59] | MCs detection | 2500 | AlexNet, SVM, DT, k-NN, NB | CBIS-DDSM, BCDR | SVM best among classical ML models. AlexNet achieved superior overall performance. |
| Liang (2022) [68] | MCs classification | 5476 | XGBoost | Private | Accuracy: 90.24%, AUC: 0.89. XGBoost outperformed several ML models. Feature engineering was critical. |
| Diaz (2014) [58] | MCs classification | 200 | SVM | Digitized mammograms | Best model: Gaussian SVM. Sensitivity: 84.0% (glandular), 87.1% (dense), 88.7% (fatty). Overall sensitivity 85.9%. |
| Prinzi (2024) [61] | MCs detect. + classif. | 758 | ML + Radiomics | Private | Best model: XGBoost. AUC: 0.83 (healthy), 0.856 (benign), 0.876 (malignant). Features align with prior clinical findings. |
| Fanizzi (2020) [62] | Classification | 260 ROIs | Rule-based | BCDR | AUC: 0.9816, Accuracy: 97.31%, Specificity: 100%. Strong discrimination with minimal features. Significant improvement (p ≤ 0.01). |
| Suhail (2018) [63] | MCCs classification | 288 ROIs | DT + classifier | DDSM | Accuracy: 91%. |
| Stelzer (2020) [128] | MCs classification | 235 | ML + texture analysis | Private | Combined texture analysis and ML effectively distinguish benign vs. malignant MCs. |
| Author, Year | Design | Images | Method | Dataset(s) | Key Findings/Metrics |
|---|---|---|---|---|---|
| Oliver (2012) [129] | MCs and MCCs detection | 602 | Dictionary-based | MIAS + Private | Sensitivity: 80% at 1 FP cluster/image (ROC and FROC analysis). |
| Quintanilla (2010) [130] | MCs detection | 100 | Enhancement + k-means | Private | Accuracy: 97.72%, Sensitivity: 98%, Specificity: 99.67%, AUC: 0.9875. |
| Brahimetaj (2022) [131] | Early MCs detection | 450 | RF, SVM, MLP, AdaBoost | Private | Random Forest performed best. Accuracy 77.03%, sensitivity 60.46%, specificity 89.77%, F1 76.35%, AUC 0.801. |
| Mahmood (2021) [99] | MCs detection + diagnosis | 322 | ML + radiomics | MIAS | AUC 0.90, sensitivity 98%, accuracy 98%. Improves diagnostic efficiency. |
| Fadil (2020) [9] | MCs classification | 966 | DWT + Random Forest | Private | Sensitivity 93%, specificity 97%, accuracy 95%, AUC 0.92. |
| Author, Year | Design | Images | Method | Dataset(s) | Key Findings/Metrics |
|---|---|---|---|---|---|
| Pesapane (2023) [69] | Detection + classification | 1986 | AlexNet, ResNet18/34 | Private | AlexNet performed best. Detection: sensitivity 98%, specificity 89%, AUC 0.98. Classification: sensitivity 85%, AUC 0.94. |
| Kang (2021) [79] | MCs classification | 1579 | ResNet | Private | Accuracy 81.54%, specificity 91.41%, PPV 81.82%. |
| Luna (2025) [11] | MCCs classification | 12,000 patches | CNN | INbreast | Accuracy 99.71% with compact model (29 k parameters). |
| Teoh (2024) [80] | MCs classification | 1500 | DL ensemble | CBIS-DDSM | Ensemble confidence: 0.9305 for MCs and 0.8859 for normal cases. |
| Honjo (2022) [83] | Image quality evaluation | 136 | DL enhancement | Private | Super-resolution mammograms significantly improved quality (PIQE, p < 0.001). |
| Wang (2017) [86] | MCCs detection | 2000 | Deep CNN | DDSM | AUC 0.971 (CNN classifier) vs. 0.944 (MC detector). Global features improve discrimination of clustered MCs. |
| Cai (2019) [87] | MCs diagnosis | 990 | CNN + SVM | Private | Precision 89.32%, sensitivity 86.89%. Deep features outperform handcrafted features. |
| Schönenberger (2021) [132] | BI-RADS classification | 268 | CNN | Private | CNNs effectively classify MCs according to BI-RADS, supporting standardized diagnosis. |
| Leong (2022) [100] | MCs detection | 322 | ResNet50 | CBIS-DDSM | Accuracy: ResNet50 97.58%, ResNet34 97.35%, VGG16 96.97%, AlexNet 83.06%. |
| Gerbesi (2023) [89] | MCs detection + classification | 1000 | DeepMiCa | Private | Automated pipeline improves detection and classification, supporting clinical decision-making and reducing unnecessary biopsies. |
| Kumar (2022) [73] | MCs classification | 1547 | CNN | CBIS-DDSM | Best accuracy 94%, sensitivity 97%, AUC 0.96 using AdaDelta optimizer. |
| Yurdusev (2023) [76] | MCs detection + classification | 500 | DL | DDSM | Accuracy 97.67%, outperforming baseline and Faster R-CNN. |
| Zhang (2019) [90] | Multi-scale detection | 450 | DL | MIAS | Accuracy 97.16%. Improves small-target detection by 5–10%. |
| Kallenberg (2016) [133] | Feature learning | 500 | Convolutional sparse autoencoder | Private | Learns discriminative features without prior assumptions; supports risk scoring. |
| Ayyadurai (2024) [134] | MCs and mass detection | 400 | ML + DL | Private | Accuracy, precision, recall, and F1-score all approximately 99%. |
| Author, Year | Design | Images | Method | Dataset(s) | Key Findings/Metrics |
|---|---|---|---|---|---|
| Hernández (2025) [10] | MCs detection + classification | 1284 | CNN + GLCM + Gabor | Multiple | Localization accuracy 73.0%, classification accuracy 73.0%. Moderate performance across metrics. |
| Rehman (2025) [96] | Mammogram classification | 80 | VGG16 | PINIM, DDSM | PINIM accuracy 96%, DDSM accuracy 95%. High sensitivity and precision across datasets. |
| Abdulqader (2025) [111] | Image synthesis comparison | 80 | Pix2Pix, SPADE GAN, WGAN | ACDC, CHAOS | SPADE GAN achieved best results: PSNR 36 dB, SSIM > 0.97, Dice 0.94, FID < 0.01. |
| Luna (2025) [81] | MCCs detection (transfer learning) | 620 | CNN | MEXbreast | Accuracy: 98.32%, 99.27%, and 89.17% for 50, 70, and 100 μm resolutions. |
| Suzuki (2017) [135] | Overview | N/A | DL | Multiple | Overview of deep learning methods and their mathematical foundations in medical imaging. |
| Wang (2016) [98] | MCs/masses discrimination | 1000 | DL | Private | Accuracy: 87.3% for MCs, 61.3% for masses, 89.7% for combined MCs, 84.8% overall. Combined analysis improves performance. |
| Hsu (2025) [84] | MCs detection + segmentation | 150 | U-Net, V-Net | Private | U-Net outperforms V-Net. Accuracy up to 85% with preprocessing. |
| Oyelade (2022) [136] | Dataset augmentation | 2781 | GAN | MIAS | Synthetic ROIs improve dataset quality and enhance DL model performance for breast cancer detection. |
| Joseph (2024) [137] | Dataset balancing | 322 | cGAN | MIAS | Class imbalance negatively affects DL performance in MC detection and classification tasks. |
| Singla (2025) [92] | Synthetic data comparison | 262,599 | VQ-VAE, GAN | MIAS | High-quality synthetic data improves model performance and reliability in medical imaging. |
| Biju (2024) [110] | Image synthesis | 60,000 | GAN | CelebA, CIFAR-10 | Inception Score: 9.69 (CelebA), 10.79 (CIFAR-10). FID: 7.91 (CelebA). Improved stability and image quality with improved loss function. |
| Shia (2024) [138] | MCs detection | 11,303 | YOLOv8 | Private | Accuracy 84.2%, F1-score 0.82, mAP 70.9%, recall 79.6%. Strong localization performance. |
| Shia (2025) [95] | MCs classification | 3674 | EfficientNet, ResNet | Private (BI-RADS 1–2,5–6) | EfficientNet models significantly outperformed ResNet architectures (p < 0.05). Best model: EfficientNet-B3 with accuracy 86.9%, AUC 0.998, weighted F1-score 0.869. No significant differences among EfficientNet variants. EfficientNet-B0 achieved comparable performance with faster inference time. Five-fold cross-validation used. |
| Wenjie (2025) [93] | DCIS vs. IDC classification | 294 cases | ResNet101 | Private | AUC 97%, accuracy 93%, sensitivity 94%, specificity 92%. Combined model outperforms individual approaches. |
| Ayşe (2023) [76] | MCs detection + classification | 500 | R-CNN, YOLOv4 | DDSM | Difference filters improve MC visibility and detection performance. |
| Liwen (2024) [122] | MCs classification | 428 | ResNet18, DenseNet121 | Private | Outperforms standalone CNN models. Grad-CAM improves interpretability and localization. |
| Banteng (2026) [77] | MCs detection + segmentation | 1500 | YOLOv7 | VinDr-Mammo + Private | Dice: 89.19 ± 0.26%, 88.76 ± 0.32%. Boundary loss improves segmentation accuracy and reduces manual intervention. |
| Ke (2024) [82] | MCCs segmentation | 500 | Swin Transformer | FFDM-DBT, CBIS-DDSM | DSC: 86.52% (DBT), 50.78% (FFDM). Strong cross-domain segmentation performance. |
| Elumalai (2026) [70] | MCs classification | N/A | ViT | CBIS-DDSM | Dual-branch Vision Transformer effectively integrates complementary feature representations for MCs classification. Achieved accuracy 96.80%, AUC 0.982. Demonstrates improved feature fusion capability for subtle MC patterns. |
| Author, Year | Design | Images | Method | Dataset(s) | Key Findings/Metrics |
|---|---|---|---|---|---|
| Al-Qdah (2005) [38] | MCCs detection | 25 | CAD system | Private (3 demographic groups) | Accuracy: 87%, 88%, 90%. Wavelet-based detection is generally effective, but dense breast tissue remains challenging. |
| Arodź (2006) [39] | MCCs detection | 50 | db4 Wavelet Transform | Private | Detection improvement: 3.9 and 2.8 (radiologist assessment). Wavelet transform-based CAD enhances MC detection in small-field mammograms. |
| Destounis (2004) [40] | CAD evaluation (FN reduction) | 318 | CAD + Double reading | Screening population | False negatives reduced from 31% to 19%. CAD improves detection of missed cancers. |
| Karale et al. (2019) [29] | MCCs detection | 180 | Multistage CAD | DDSM + INbreast + PGIMER-IITKGP | Two-dimensional NEO method shows superior sensitivity and false-positive performance, especially on PGIMER-IITKGP dataset. |
| Songyang (2000) [139] | MCCs detection | 20 | CAD system | Nijmegen | Sensitivity 90%, false positives 0.5 per image. Further validation with larger datasets is required. |
| Hayat (2014) [56] | MCs detection | 181 | CAD system (k-NN, SVM, ANN) | MIAS | SVM achieved the best performance with 83% accuracy, improving diagnostic performance. |
| Mabrouk (2019) [140] | CAD framework | 181 | ML-based CAD | MIAS | Accuracy 96% (integrated features) and 97% (invariant moments with ANN). |
| Shiri (2022) [141] | MCs detection | 815 | DL-based CAD | Private | Accuracy 96.7%, sensitivity 96.7%, specificity 96.7%, AUC 0.988. |
| Loizidou (2020) [96] | MCs detection + classification | 320 | SVM-based CAD | Private | Accuracy improved from 91.42% to 99.55% using temporal subtraction (p < 0.005). |
| Rehman (2021) [74] | MCs detection | 6453 | FC-DSCNN CAD | DDSM, PINUM | Detection score up to 0.97. True positive rate 0.99 (2.45 false positives per image). Strong performance but sensitive to preprocessing quality. |
| Savelli (2020) [60] | Thesis | 500 | DL-based CAD | Private | PhD thesis on deep learning-based CAD systems. |
| Sarvestani (2023) [85] | Image enhancement | 250 | ML-based CAD | DDSM | Sensitivity 95.7%, specificity 91.5%, precision 89.3%, accuracy 93%. |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Ochoa Domínguez, H.d.J.; Luna Lozoya, R.S.; Cruz Sánchez, V.G.; Vergara Villegas, O.O.; Sossa Azuela, J.H.; Santiago Ramirez, E. AI-Driven Microcalcification Detection in Digital Mammography for Early Breast Cancer Diagnosis: A Scoping Review, Challenges, Limitations, and Future Perspectives. Mathematics 2026, 14, 2367. https://doi.org/10.3390/math14132367
Ochoa Domínguez HdJ, Luna Lozoya RS, Cruz Sánchez VG, Vergara Villegas OO, Sossa Azuela JH, Santiago Ramirez E. AI-Driven Microcalcification Detection in Digital Mammography for Early Breast Cancer Diagnosis: A Scoping Review, Challenges, Limitations, and Future Perspectives. Mathematics. 2026; 14(13):2367. https://doi.org/10.3390/math14132367
Chicago/Turabian StyleOchoa Domínguez, Humberto de Jesús, Ricardo Salvador Luna Lozoya, Vianey Guadalupe Cruz Sánchez, Osslan Osiris Vergara Villegas, Juan Humberto Sossa Azuela, and Everardo Santiago Ramirez. 2026. "AI-Driven Microcalcification Detection in Digital Mammography for Early Breast Cancer Diagnosis: A Scoping Review, Challenges, Limitations, and Future Perspectives" Mathematics 14, no. 13: 2367. https://doi.org/10.3390/math14132367
APA StyleOchoa Domínguez, H. d. J., Luna Lozoya, R. S., Cruz Sánchez, V. G., Vergara Villegas, O. O., Sossa Azuela, J. H., & Santiago Ramirez, E. (2026). AI-Driven Microcalcification Detection in Digital Mammography for Early Breast Cancer Diagnosis: A Scoping Review, Challenges, Limitations, and Future Perspectives. Mathematics, 14(13), 2367. https://doi.org/10.3390/math14132367