1. Introduction
Physical anthropomorphic breast models are increasingly vital for advancing novel imaging techniques, refining reconstruction methods, and assessing prototypes and could be exploited to check the performance of X-ray apparatuses [
1,
2,
3]. However, manufacturing these phantoms remains a significant challenge, particularly regarding the selection of 3D printing materials, hardware, and fabrication techniques. Current methods often rely on fused filament fabrication (FFF) to translate DICOM datasets into physical objects [
4,
5,
6,
7,
8]. One common strategy involves using a single material, such as polylactic acid (PLA), and varying the infill density and patterns to mimic the computed tomography (CT) numbers of human tissue.
Alternatively, some researchers propose using multiple materials at a 100% infill density [
9,
10]. This method is often more intuitive for non-engineers, such as radiologists, as it directly maps specific filaments to corresponding biological tissues. For breast imaging, phantoms can be produced using two filaments with X-ray attenuation corresponding to real adipose and glandular tissues. In this study, we specifically explore two “adipose–gland” material combinations: acrylic styrene acrylonitrile and high-impact polystyrene (ASA-HIPS) and Acrylic styrene acrylonitrile and acrylonitrile butadiene styrene (ASA-ABS). Based on previously reported CT attenuation characteristics and energy-dependent behavior, ASA was identified as a candidate for glandular tissue, whereas HIPS and ABS were selected as candidates for adipose tissue [
11,
12,
13,
14,
15].
The standard workflow involves segmenting tissues using commercial or custom software to generate stereolithography or Standard Tessellation Language (STL) files for the 3D printer. However, this process often introduces structural defects, such as gaps between different printed tissues [
7]. A primary cause of these errors is the reliance on off-the-shelf software or standard functions—most notably the Marching Cubes algorithm (often used via the
isocaps or
isosurface functions in MATLAB)—to convert voxel matrices into surface meshes. To avoid the drawbacks of inherent isosurface creation, we developed an alternative MATLAB script that respects the prismatic shape of every individual voxel [
16]. By preserving the original voxel geometry during the STL export process, we ensure a seamless interface between different segmented tissues, eliminating the gaps typically observed in mesh-based reconstructions.
The primary aim of this work was to evaluate four distinct methodologies for developing radiological breast phantoms by assessing their performance across various X-ray imaging techniques. Utilizing a patient-derived MRI dataset, we fabricated four phantoms based on the same digital model to determine the most effective fabrication workflow. A central focus of this evaluation is the comparison between the standard, well-established STL preparation method and our proposed voxel-preserving approach. To provide a comprehensive assessment, these two digital workflows were applied to our two material combinations: ASA-HIPS and ASA-ABS. By subjecting the resulting models to a multimodality analysis, we evaluated their structural fidelity and radiological performance, providing a framework for the fabrication and assessment of high-fidelity anthropomorphic breast phantoms.
2. Materials and Methods
2.1. Patient Data
All four phantoms were based on the same patient data. The data were derived from a contrast-enhanced T1-weighted breast MRI examination performed on a Siemens Verio MRI scanner (Siemens Healthineers, Erlangen, Germany), approved by the Ethics Committee of the Medical University of Varna (Approval No. 102/22.04.2021).
The T1-weighted sequence was further processed, and each of the 187 image slices was semi-automatically segmented into adipose and glandular tissue. The pixel size in each slice was 1.04 mm × 1.04 mm, while the slice thickness was 1.3 mm. Post-processing was also performed in MATLAB (R2022a) using morphological operations in order to improve the overall segmentation. For this purpose, a cubic structuring element with dimensions of 2 × 2 × 2 voxels was used as the neighboring kernel. Specifically, a closing operation was performed in order to remove discontinuities and to fill minor holes within the segmented tissues, while an opening operation was used to remove the isolated voxels.
Final refinement of the segmentations was performed manually in order to delineate the overall breast shape, thus creating the skin. The glandular tissue properties were also assigned to the skin layer, thus finalizing the phantom as a two-component (tissue) breast computer model. No lesion was present in the patient data, and no such formation was subsequently included in the resulting computer model.
2.2. Phantoms
Although all four phantoms were based on the same patient data, they differed in the parameters and the approach used for STL file generation. Each phantom was 1 cm thick and was based on the same breast section from the patient data. The combinations used to generate the four phantoms are summarized in
Table 1.
For STL generation, we made use of two export procedures, referred to as EP1 and EP2, both implemented in MATLAB (R2022a). The EP1 approach uses a MATLAB script by Sven Holocombe [
17] to create the STL file from the segmented patient data. The EP2 approach uses an in-house script developed to convert voxel-based models into STL files [
16] and to overcome the limitations of conventional isosurface-based mesh generation when applied to multi-material 3D printing. Each voxel is treated as a rectangular prism. During the generation of meshes, the boundary faces separating a segmented region from the surrounding background or from another tissue type are identified, while internal faces shared by adjacent voxels of the same segment are discarded. Each remaining rectangular boundary face is then divided into two triangular facets, with outward-oriented normal vectors assigned consistently. By directly converting voxel boundaries into triangular surface elements, the generated STL model accurately reproduces the original segmentation and avoids the small gaps and overlaps that may arise from conventional isosurface extraction methods. This results in watertight surfaces with geometrically consistent interfaces between neighboring tissues, particularly important for multi-material 3D printing.
Furthermore, two material combinations were explored, with the materials selected based on their properties and their ability to mimic the corresponding breast tissue types [
12]. The first material combination consisted of ASA and HIPS for glandular and adipose tissue, respectively. The second combination consisted of ASA for glandular tissue and ABS for adipose tissue.
Finally, two FFF 3D printers were used to print the phantoms, and the STL files were sliced using their dedicated slicing software. Namely, these were the Raise3D Pro3 Plus 3D printer (Raise3D, Shanghai, China), used with the IdeaMaker (5.3.2.8640) slicing software, and the Bambu Lab P1S (Bambu Lab, Shenzhen, China), used with the Bambu Studio (v2.4.0) slicing software.
A 0.6 mm nozzle was used with the Bambu Lab P1S printer in order to improve the extrusion stability during printing. Preliminary prints showed material build-up and nozzle clogging. Therefore, a larger nozzle was selected to improve the extrusion reliability and reduce the risk of clogging. A monotonic internal solid infill pattern with a 100% infill density and a cross-hatch infill pattern were chosen. Other notable changes from the default settings included reducing the number of wall loops to one, selecting the Arachne wall generator, and setting the infill/wall overlap to 50%. Printing speeds were also adjusted, with the inner wall, internal solid infill, and top surface speeds set to 120 mm/s. The temperature for the textured PEI plate was set to 90 °C. The nozzle temperature was set to 260 °C for the initial layers and 270 °C for the remaining layers in the case of ABS. The flow ratio was set to 91%. For ASA, the nozzle temperatures for the initial layers and remaining layers were set to 260 °C and 265 °C, respectively. The flow ratio was set to 89%. The layer height was set to 0.30 mm.
Similarly, for the Raise3D printer, a 0.6 mm nozzle was used. The heated bed temperature was maintained at 74 °C with cooling fans disabled. The ASA and HIPS materials were printed using the dual extruder configuration. The extrusion temperature was set to 243 °C for ASA and 255 °C for HIPS. Flow rates were set to 91% and 93%, respectively. The printing was performed using a rectilinear infill pattern and a single perimeter, with the printing speed set to 50 mm/s. Furthermore, the printing settings included 100% infill with 25% infill overlap and a layer height of 0.25 mm.
2.3. Imaging Techniques
The evaluation of the fabricated phantoms was accomplished using two clinical systems—a clinical CT scanner, namely the Siemens SOMATOM Force (Siemens Healthineers, Erlangen, Germany), and a clinical mammography unit, the GE Senographe Pristina (GE HealthCare, Chicago, IL, USA), which was used in both 2D mode (mammography) and 3D mode (digital breast tomosynthesis). A summary of the imaging modalities and their general acquisition parameters is provided in
Table 2. All phantoms were imaged at identical conditions for a given modality.
2.4. Evaluation
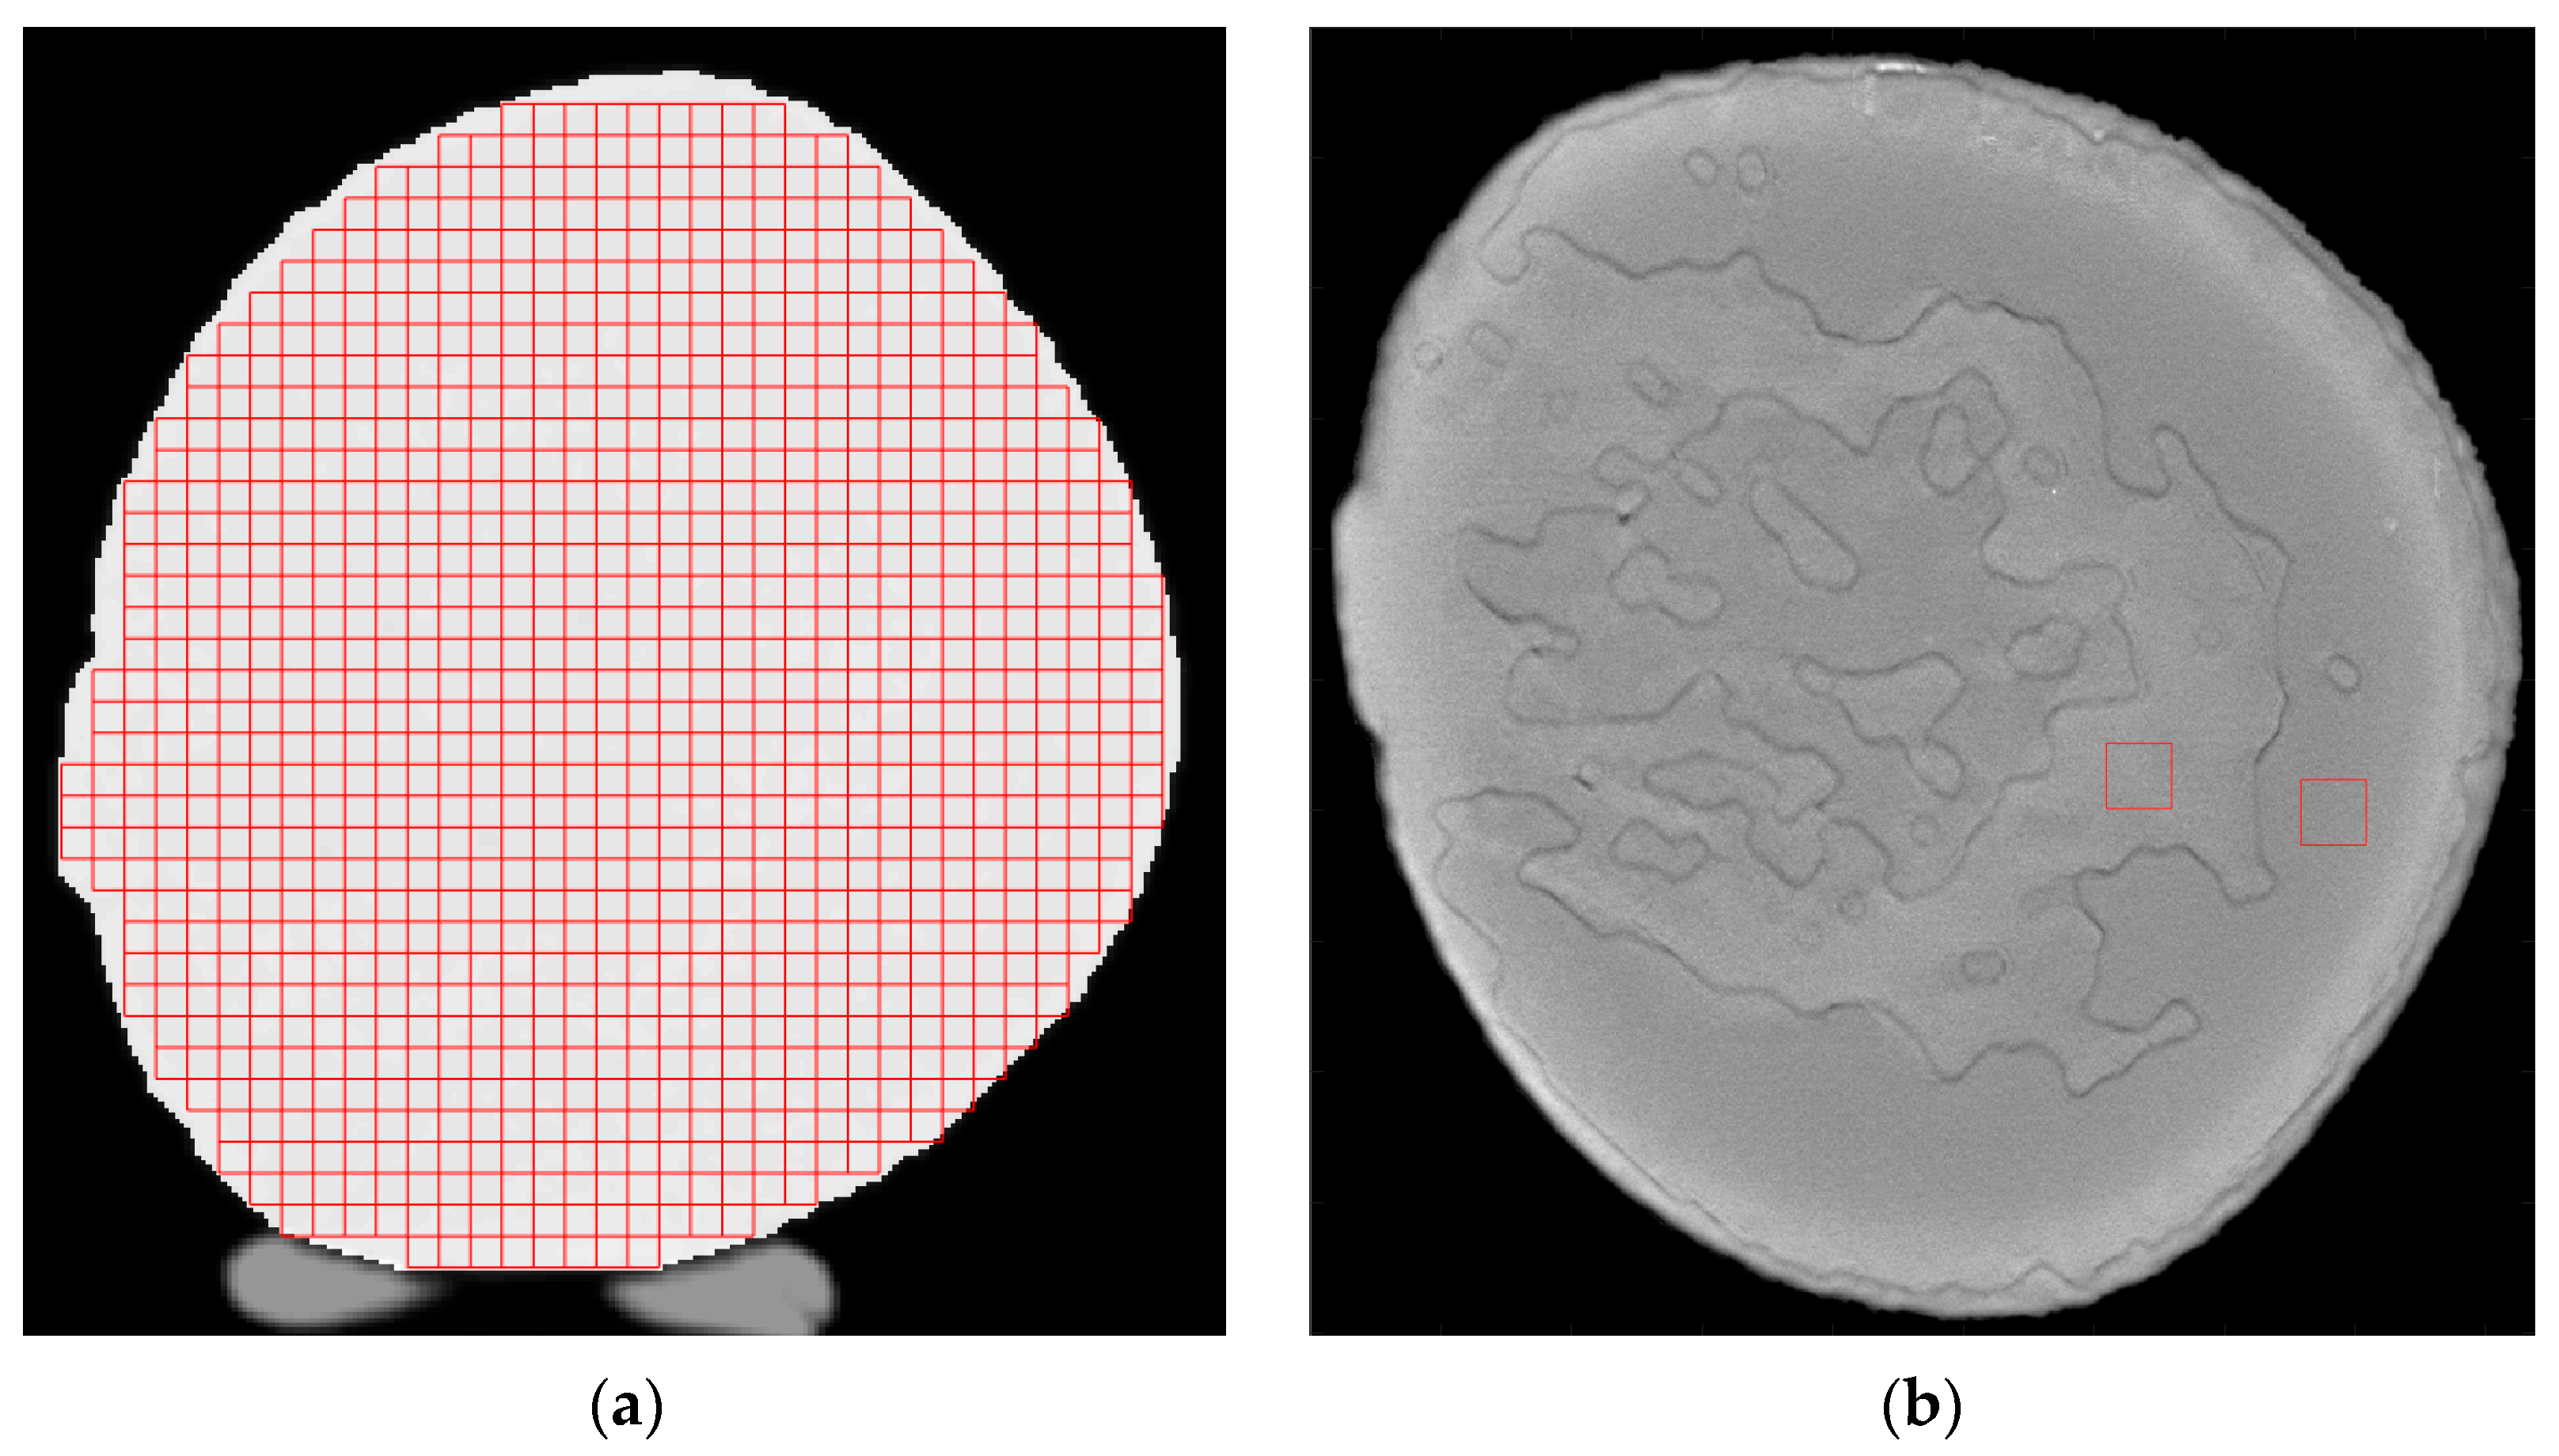
The phantoms were evaluated through both visual and quantitative comparisons of the images obtained using each modality. For the quantitative analysis, histograms of breast region intensities were generated and compared using custom software [
18]. This process utilized regions of interest (ROIs) of 50 × 50 pixels with 50% overlap across the entire breast area for the mammography and digital breast tomosynthesis (DBT) acquisitions. In the case of CT, the ROIs were 11 × 11 pixels with 50% overlap across the entire breast area. Since the pixel size in CT is larger than in mammography and DBT, the number of pixels per ROI was recalculated. This ensured that the ROIs represented the same physical area of the object across all imaging modalities, despite the smaller pixel sizes in mammography and DBT necessitating a higher pixel count for the same region. Additionally, the contrast, contrast-to-noise ratio (CNR), and signal-to-noise ratio (SNR) were calculated using single ROIs placed within representative regions corresponding to adipose and glandular tissues for each phantom and compared among the phantoms within each modality. Examples for the different ROIs are shown in
Figure 1.
The contrast was calculated following the formula:
The contrast-to-noise ratio was calculated using the following formula:
Finally, the signal-to-noise ratio was calculated using the following formula:
For CT images, the HU values were shifted by +1000 in order to account for 0 HU, which does not represent zero attenuation. Thus, the Weber contrast (1) was calculated using Meangland + 1000 and Meanfat + 1000, while the SNR (3) was calculated using Meangland + 1000. The CNR calculation (2) was not affected by this offset, as adding a constant does not change the difference between their mean values.
3. Results
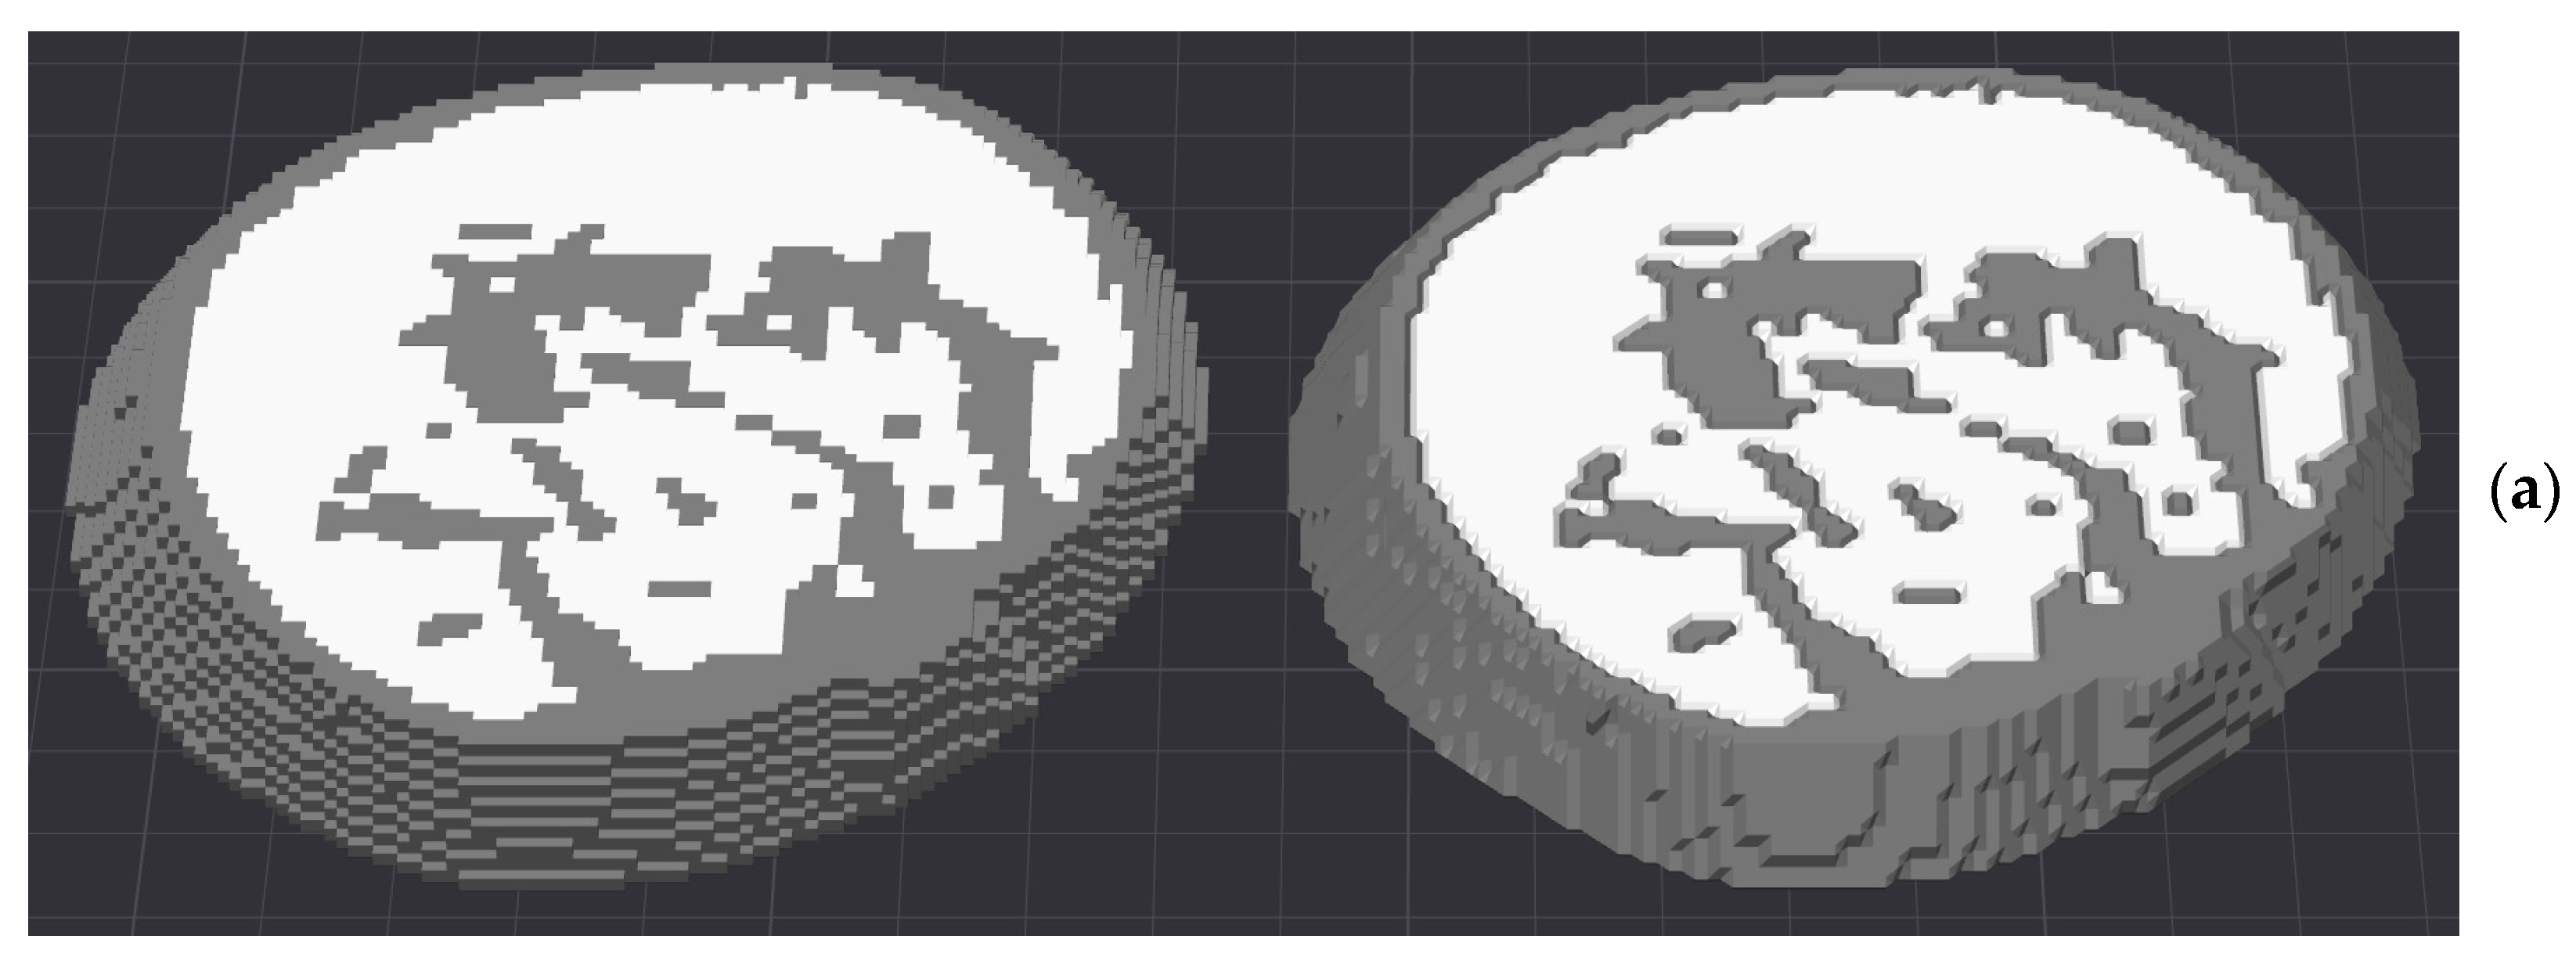
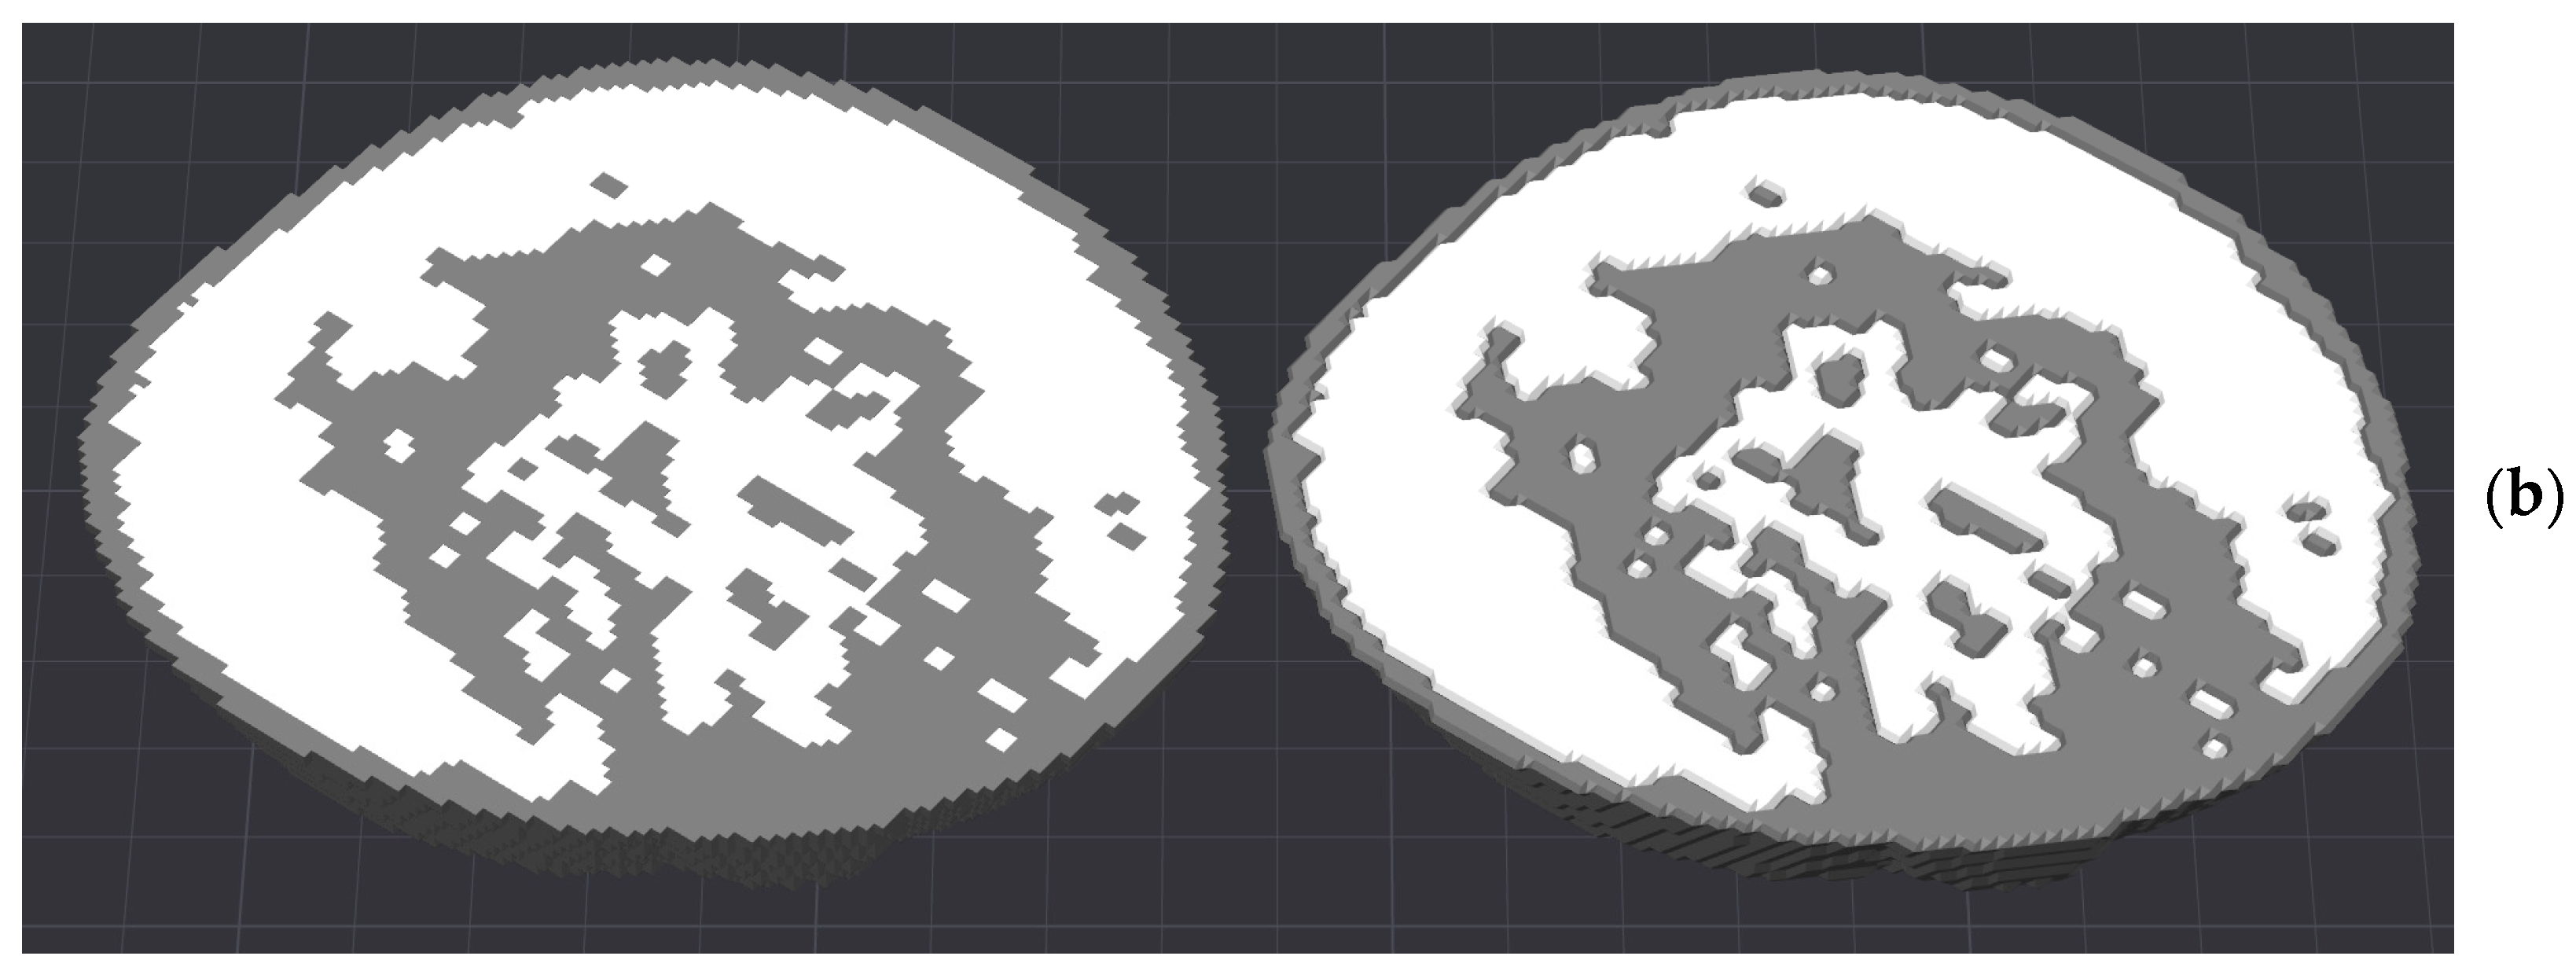
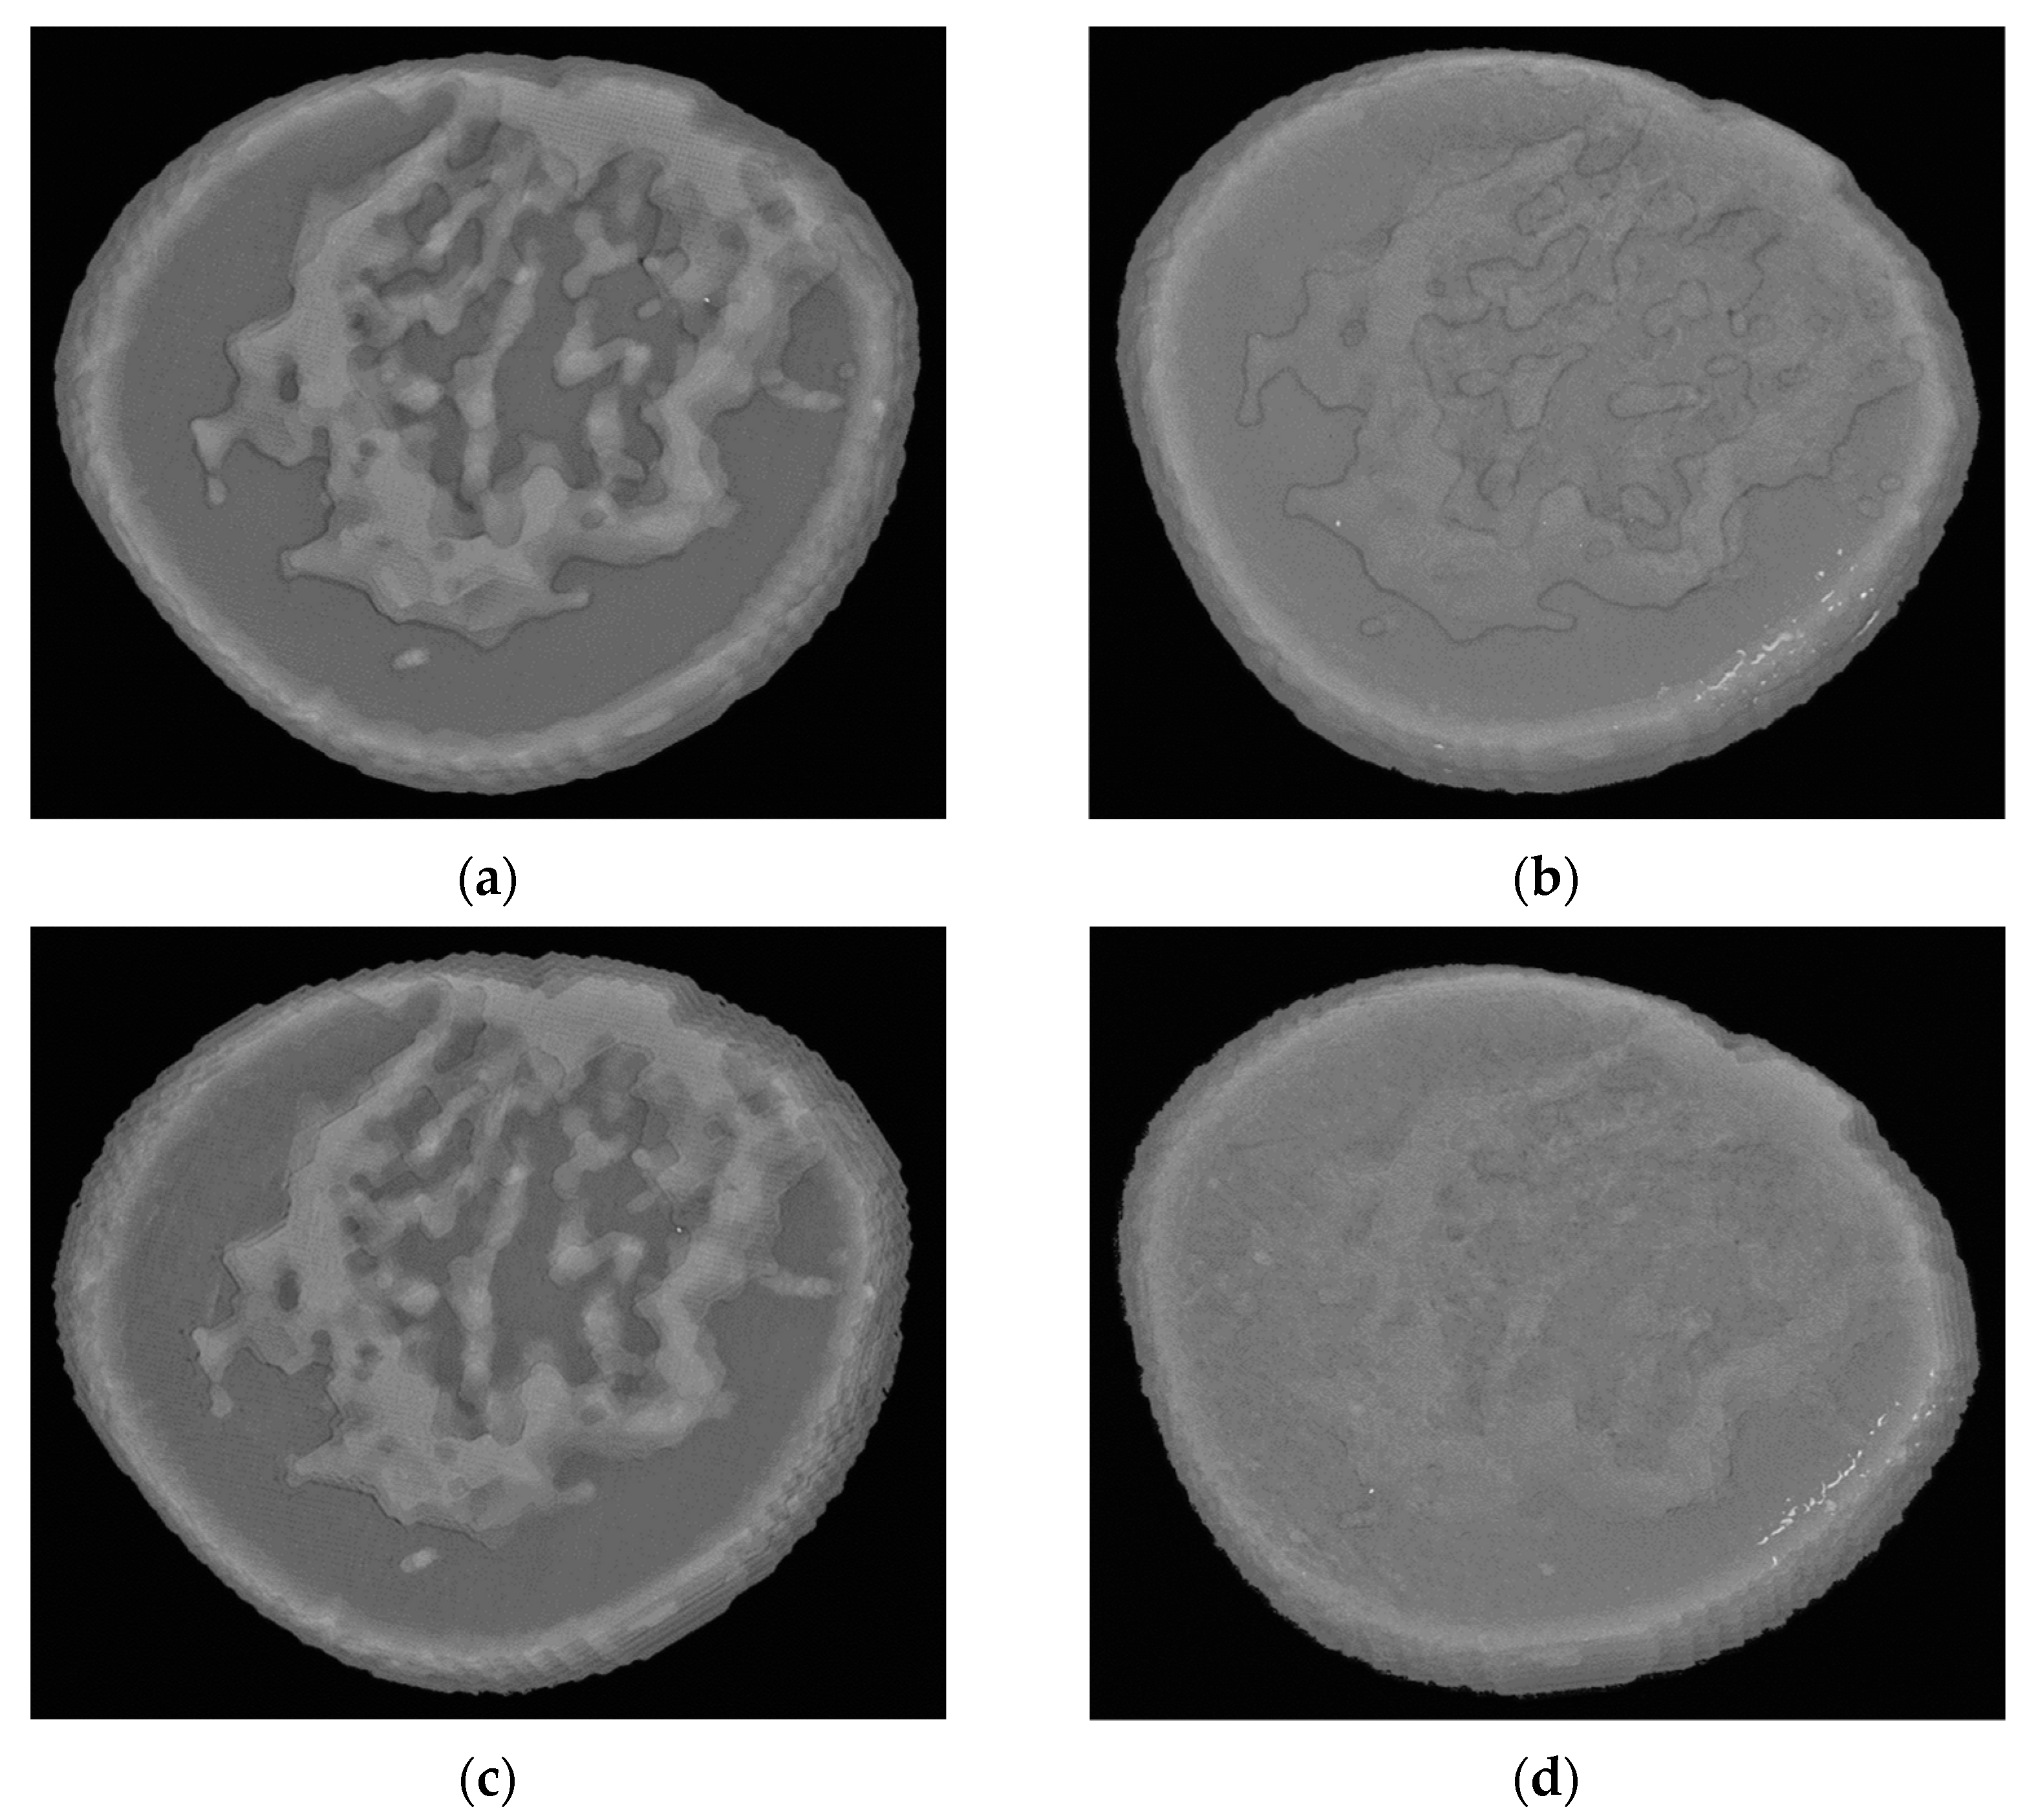
Figure 2 shows the computer models created with EP1 (right) and EP2 (left) from the top (
Figure 2a) and from the bottom (
Figure 2b). Selected slices printed from these computer breast models are shown in
Figure 3.
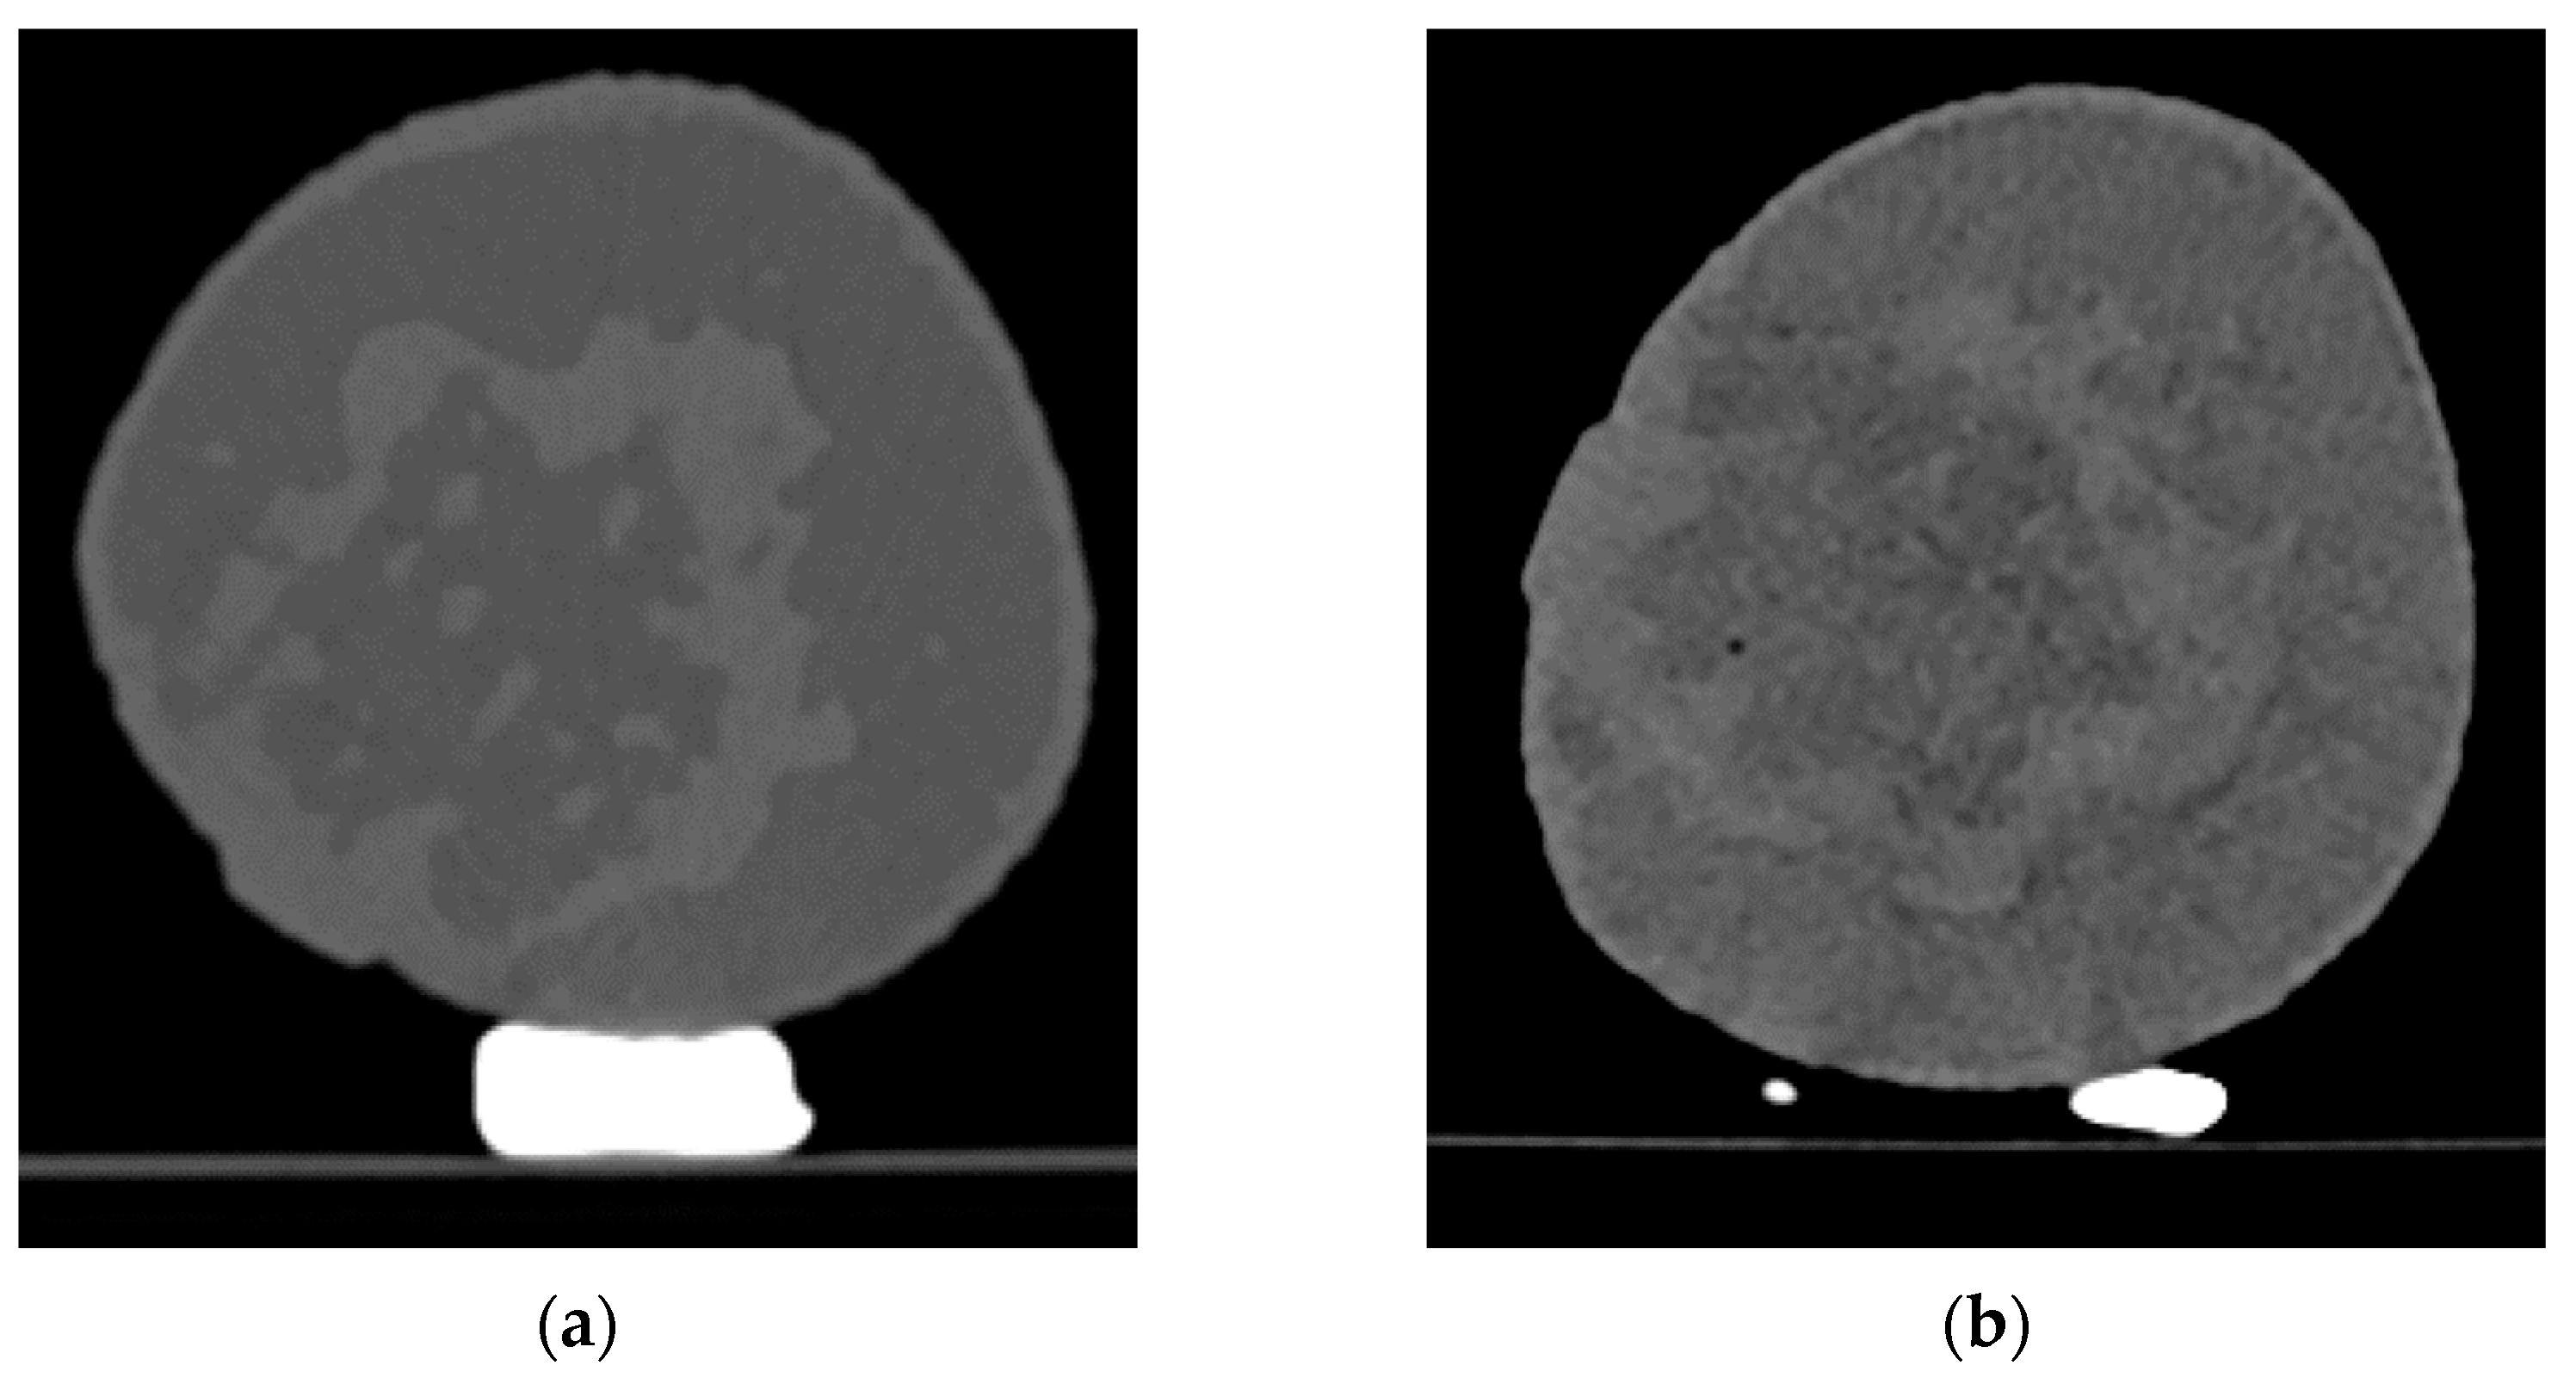
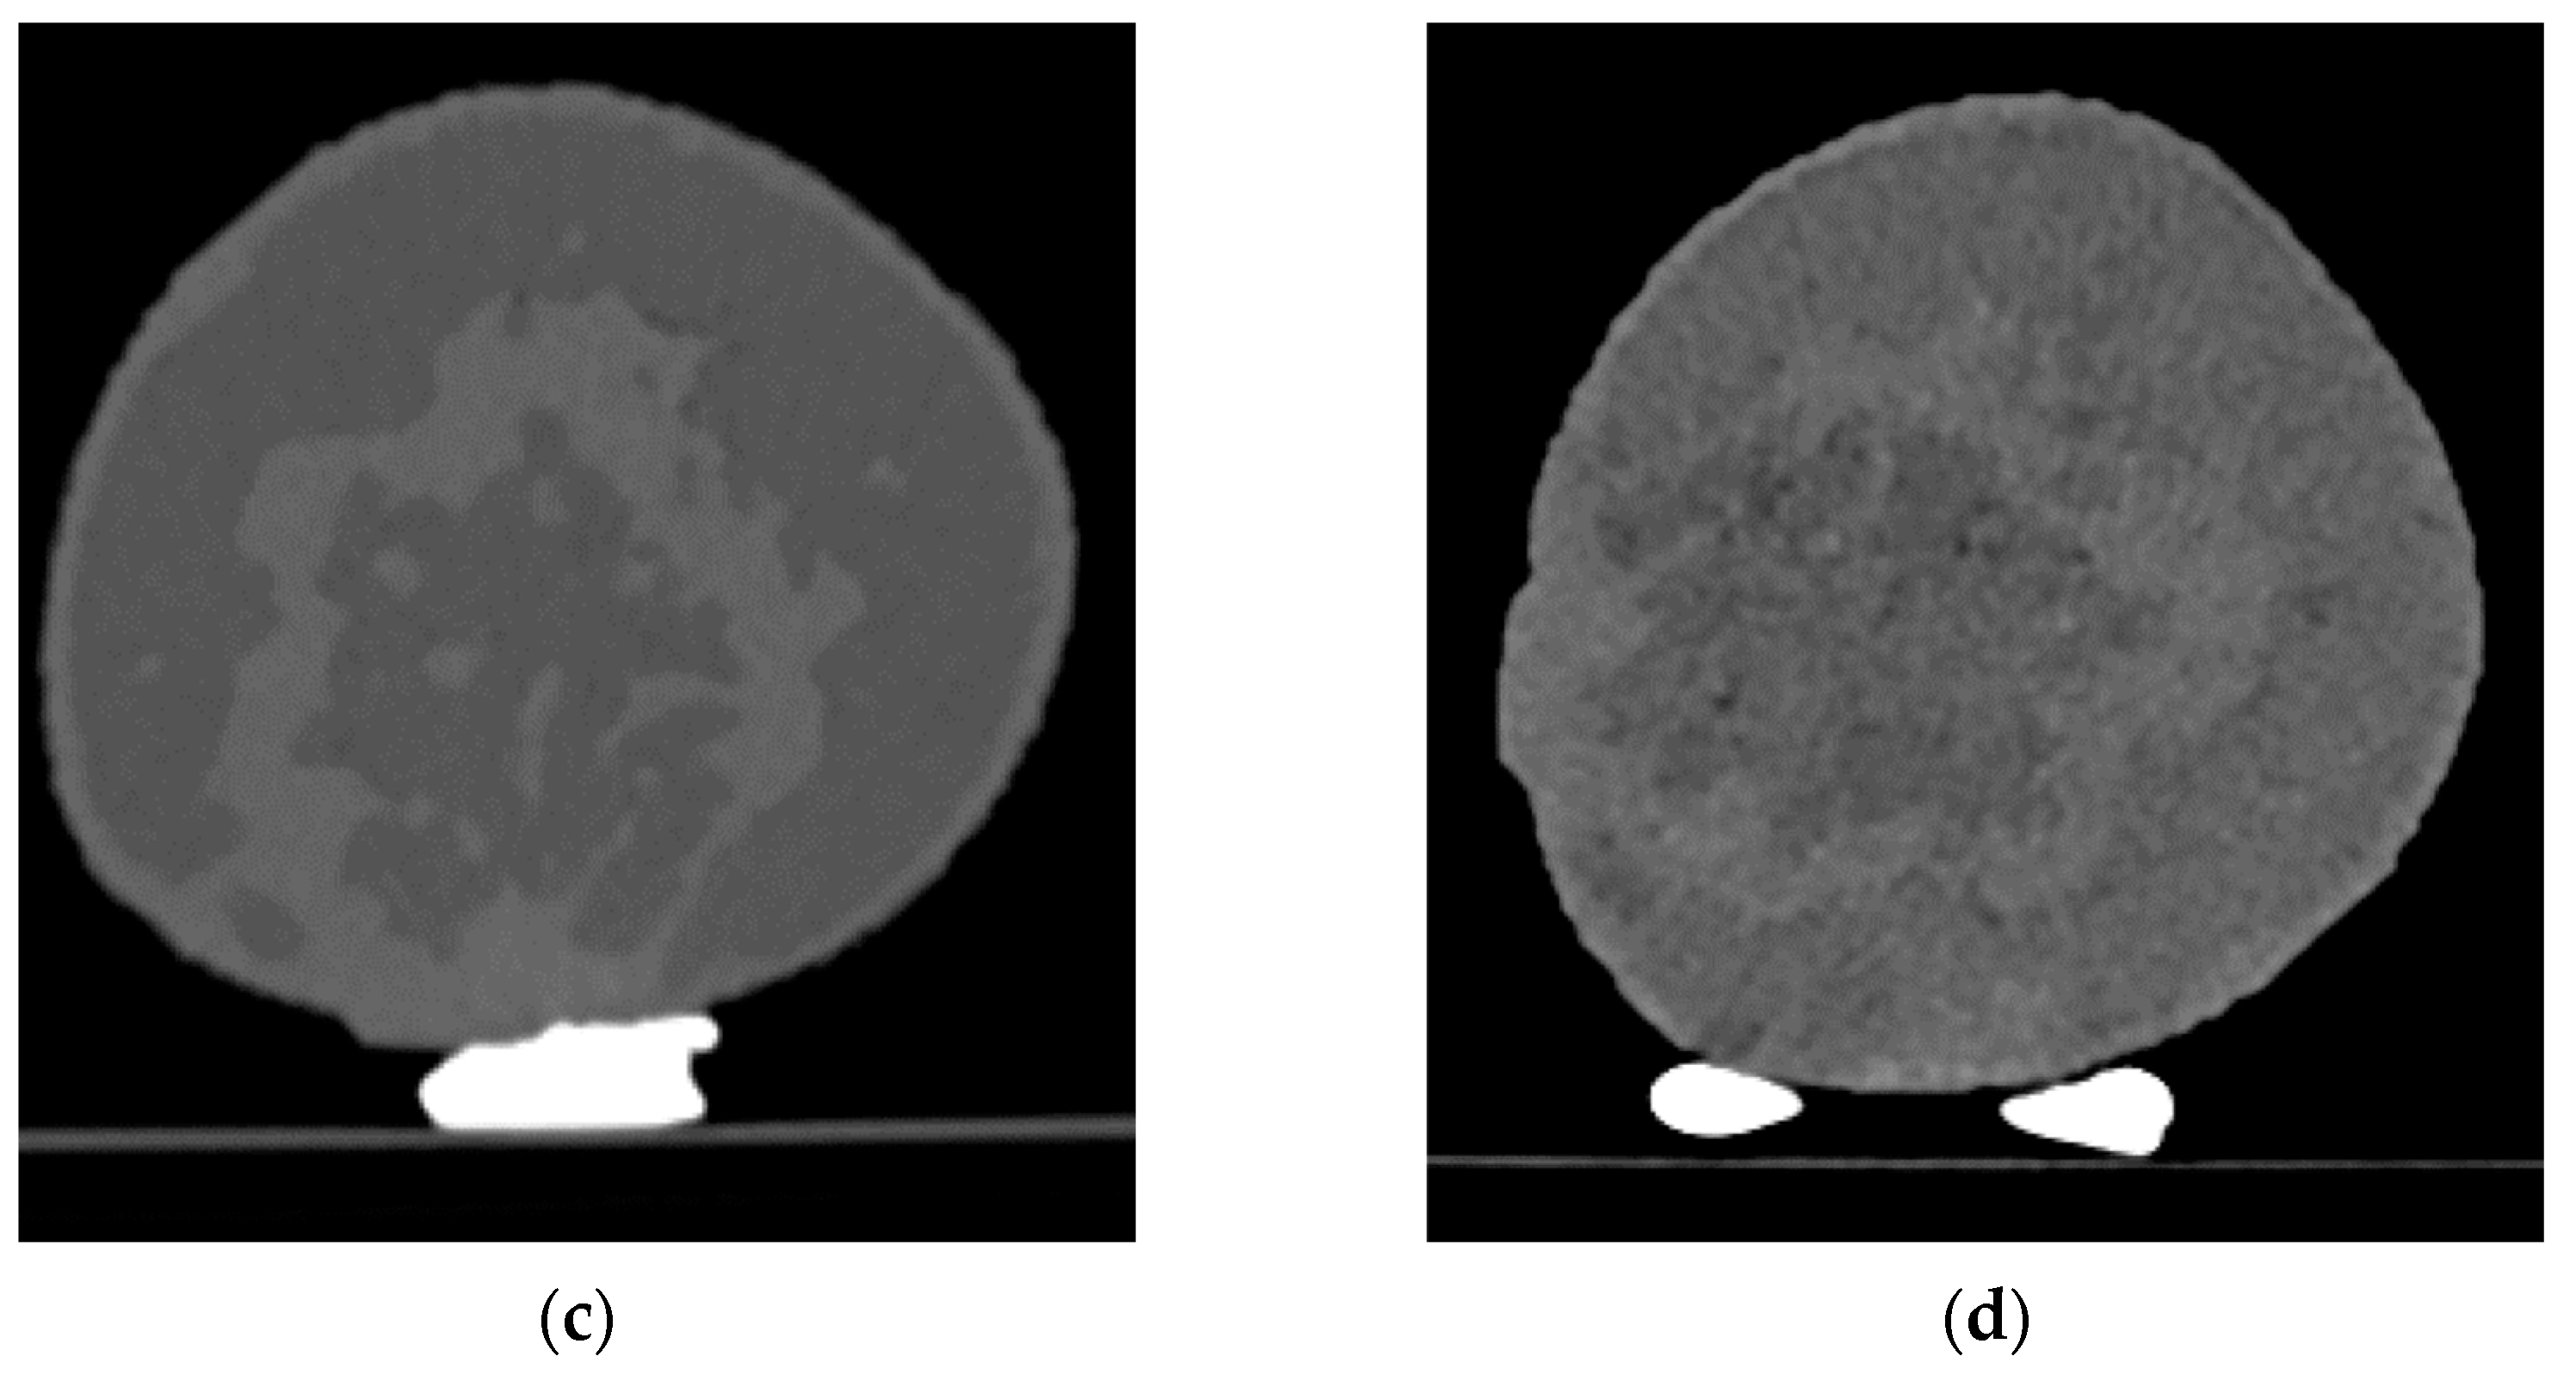
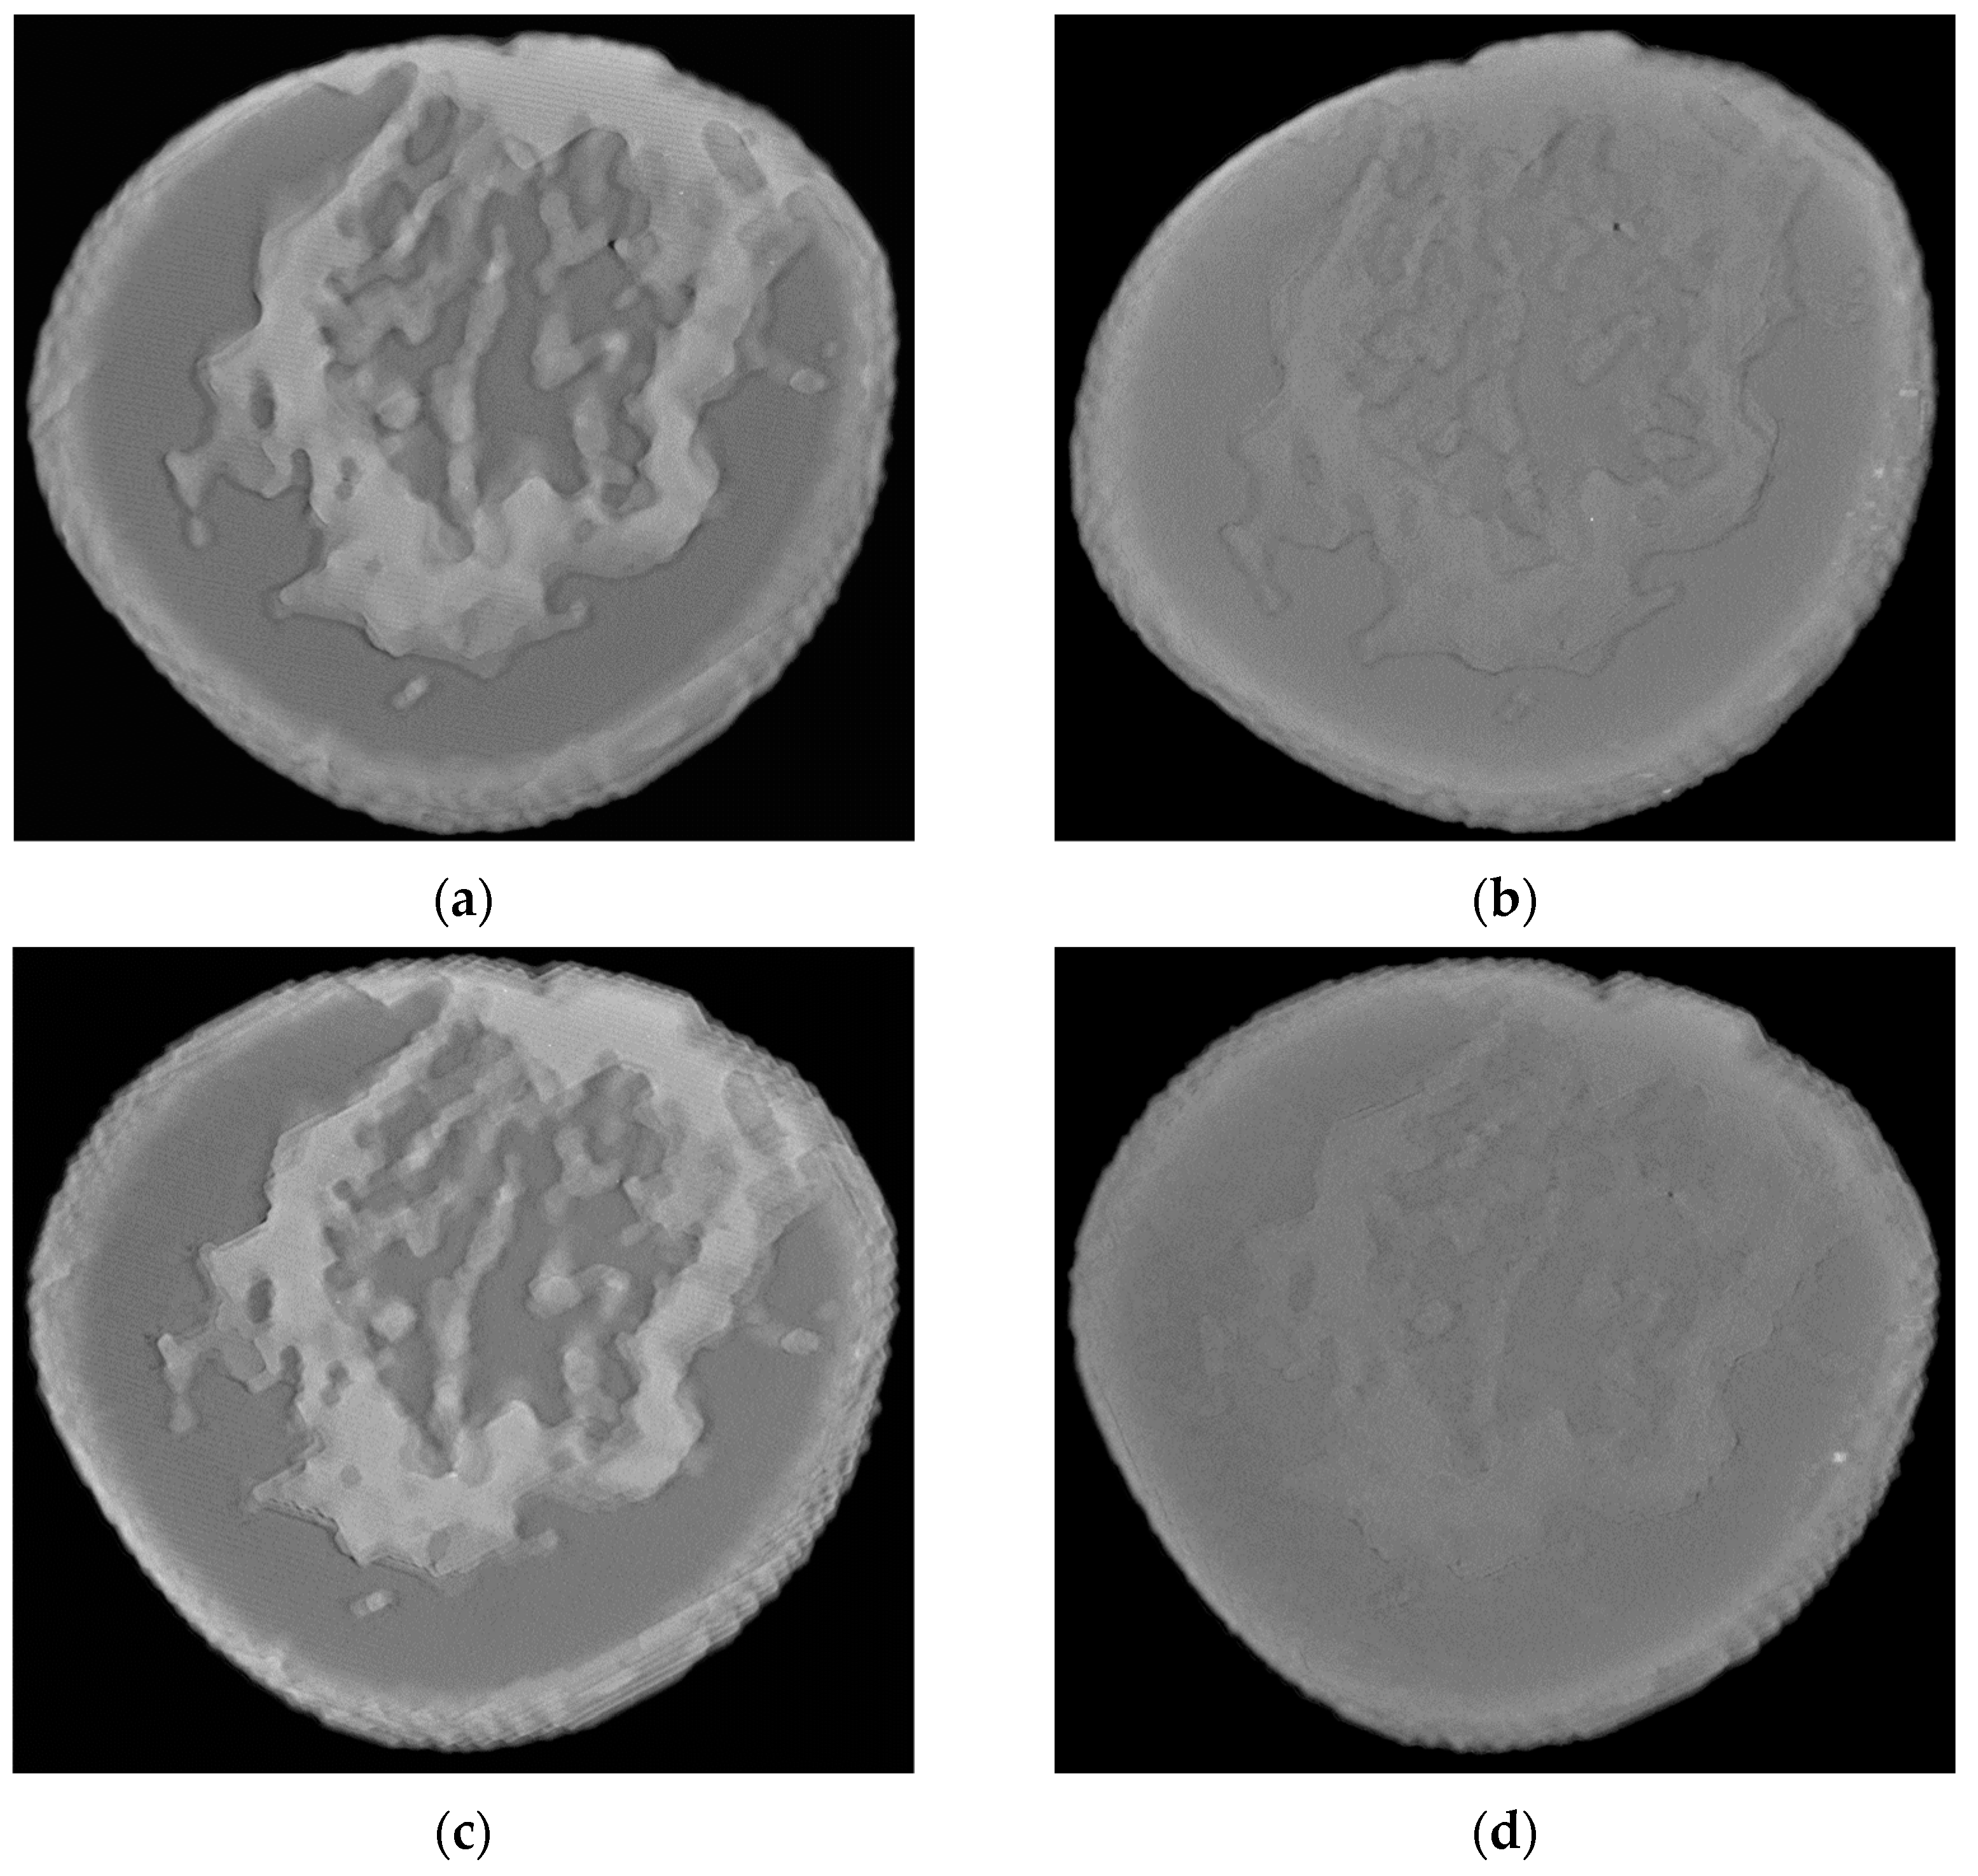
Representative images of the four phantoms, acquired with CT, DBT, and mammography, are shown in
Figure 4,
Figure 5 and
Figure 6, respectively.
The calculated values for the Weber contrast, CNR, and SNR for the three imaging modalities used to image the four phantoms are summarized in
Table 3.
Overall, the comparison of the phantoms fabricated using the EP1 STL export procedure (BP1 and BP2) and the EP2 (custom) STL export procedure (BP3 and BP4) demonstrated limited effects across all imaging modalities.
On the other hand, the printer and material combination produced substantial differences across the contrast-based imaging metrics. Phantoms printed using the Raise3D device with the ASA-HIPS materials (BP1 and BP3) consistently demonstrated higher values than those printed using the Bambu Lab printer with the ASA-ABS materials (BP2 and BP4). Specifically, the Bambu-produced phantoms showed a 73% reduction in Weber contrast for mammography, an approximately 87% reduction in Weber contrast for DBT, and an approximately 74% reduction in the mammography CNR. These results indicate that the printer–material configuration influences the imaging performance. This finding is in agreement with the work of Belarra et al. [
19], who reported that ABS more closely matches the attenuation properties of CIRS fat material than HIPS under mammographic imaging conditions.
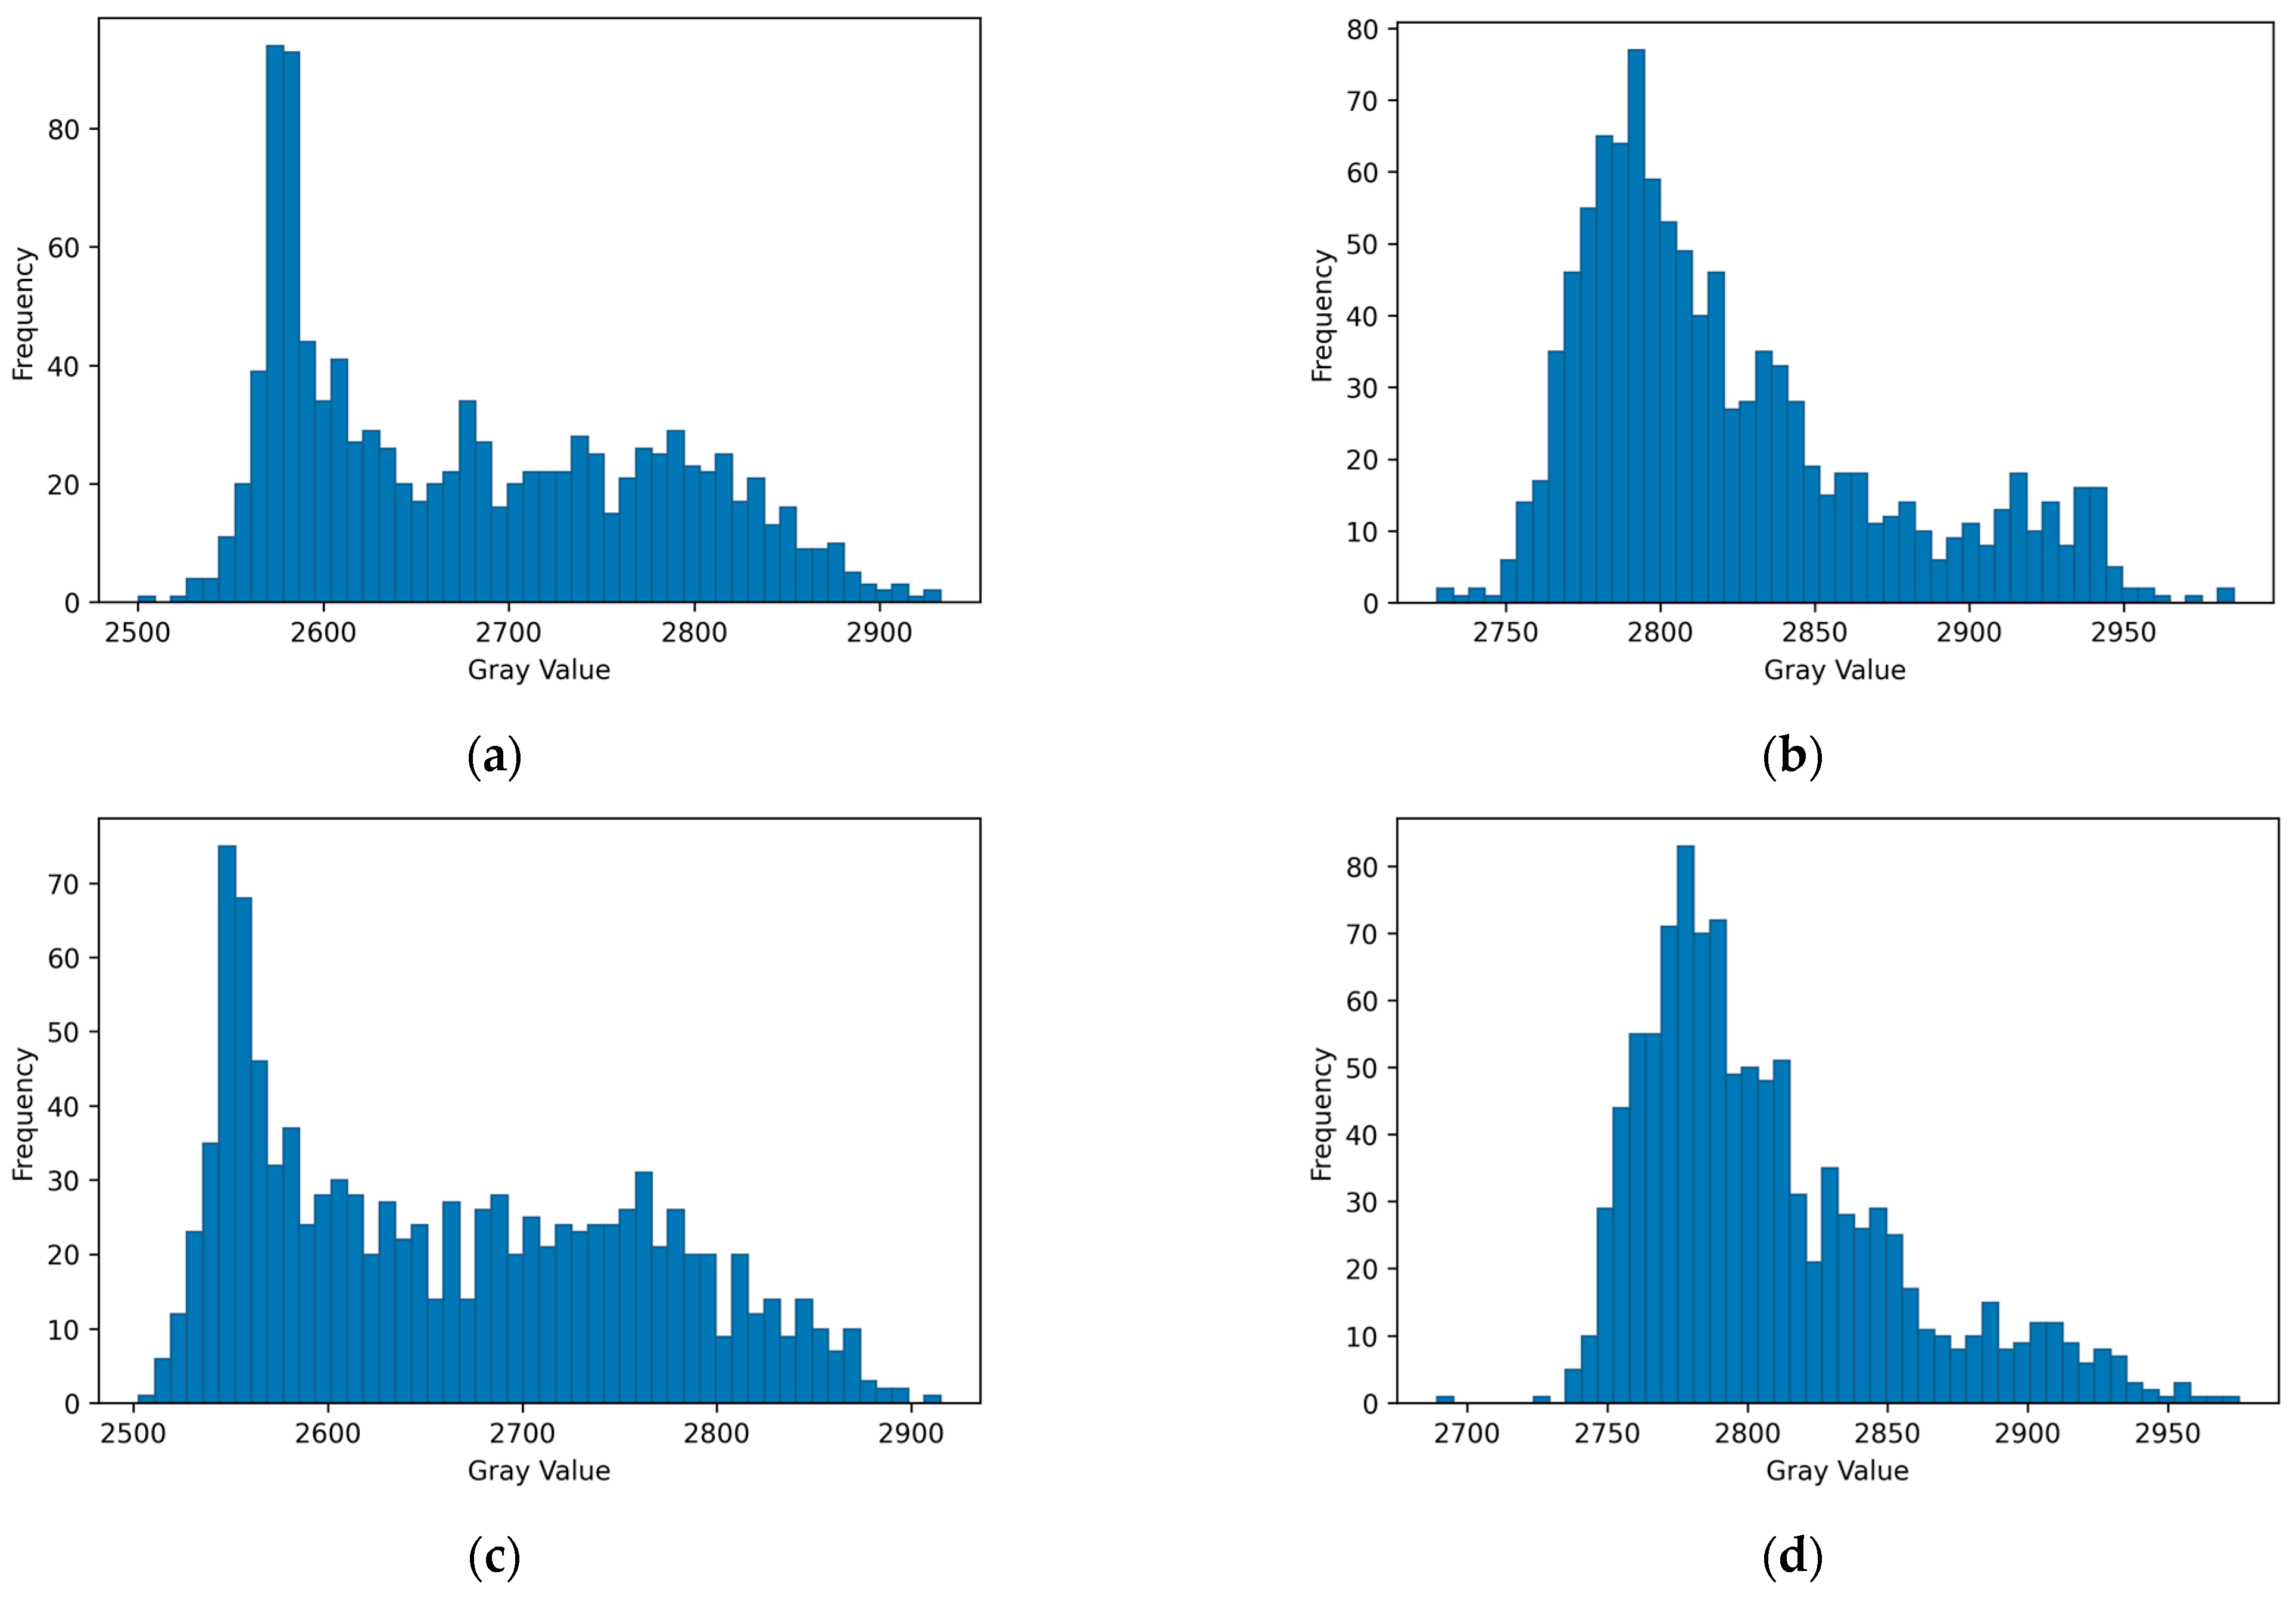
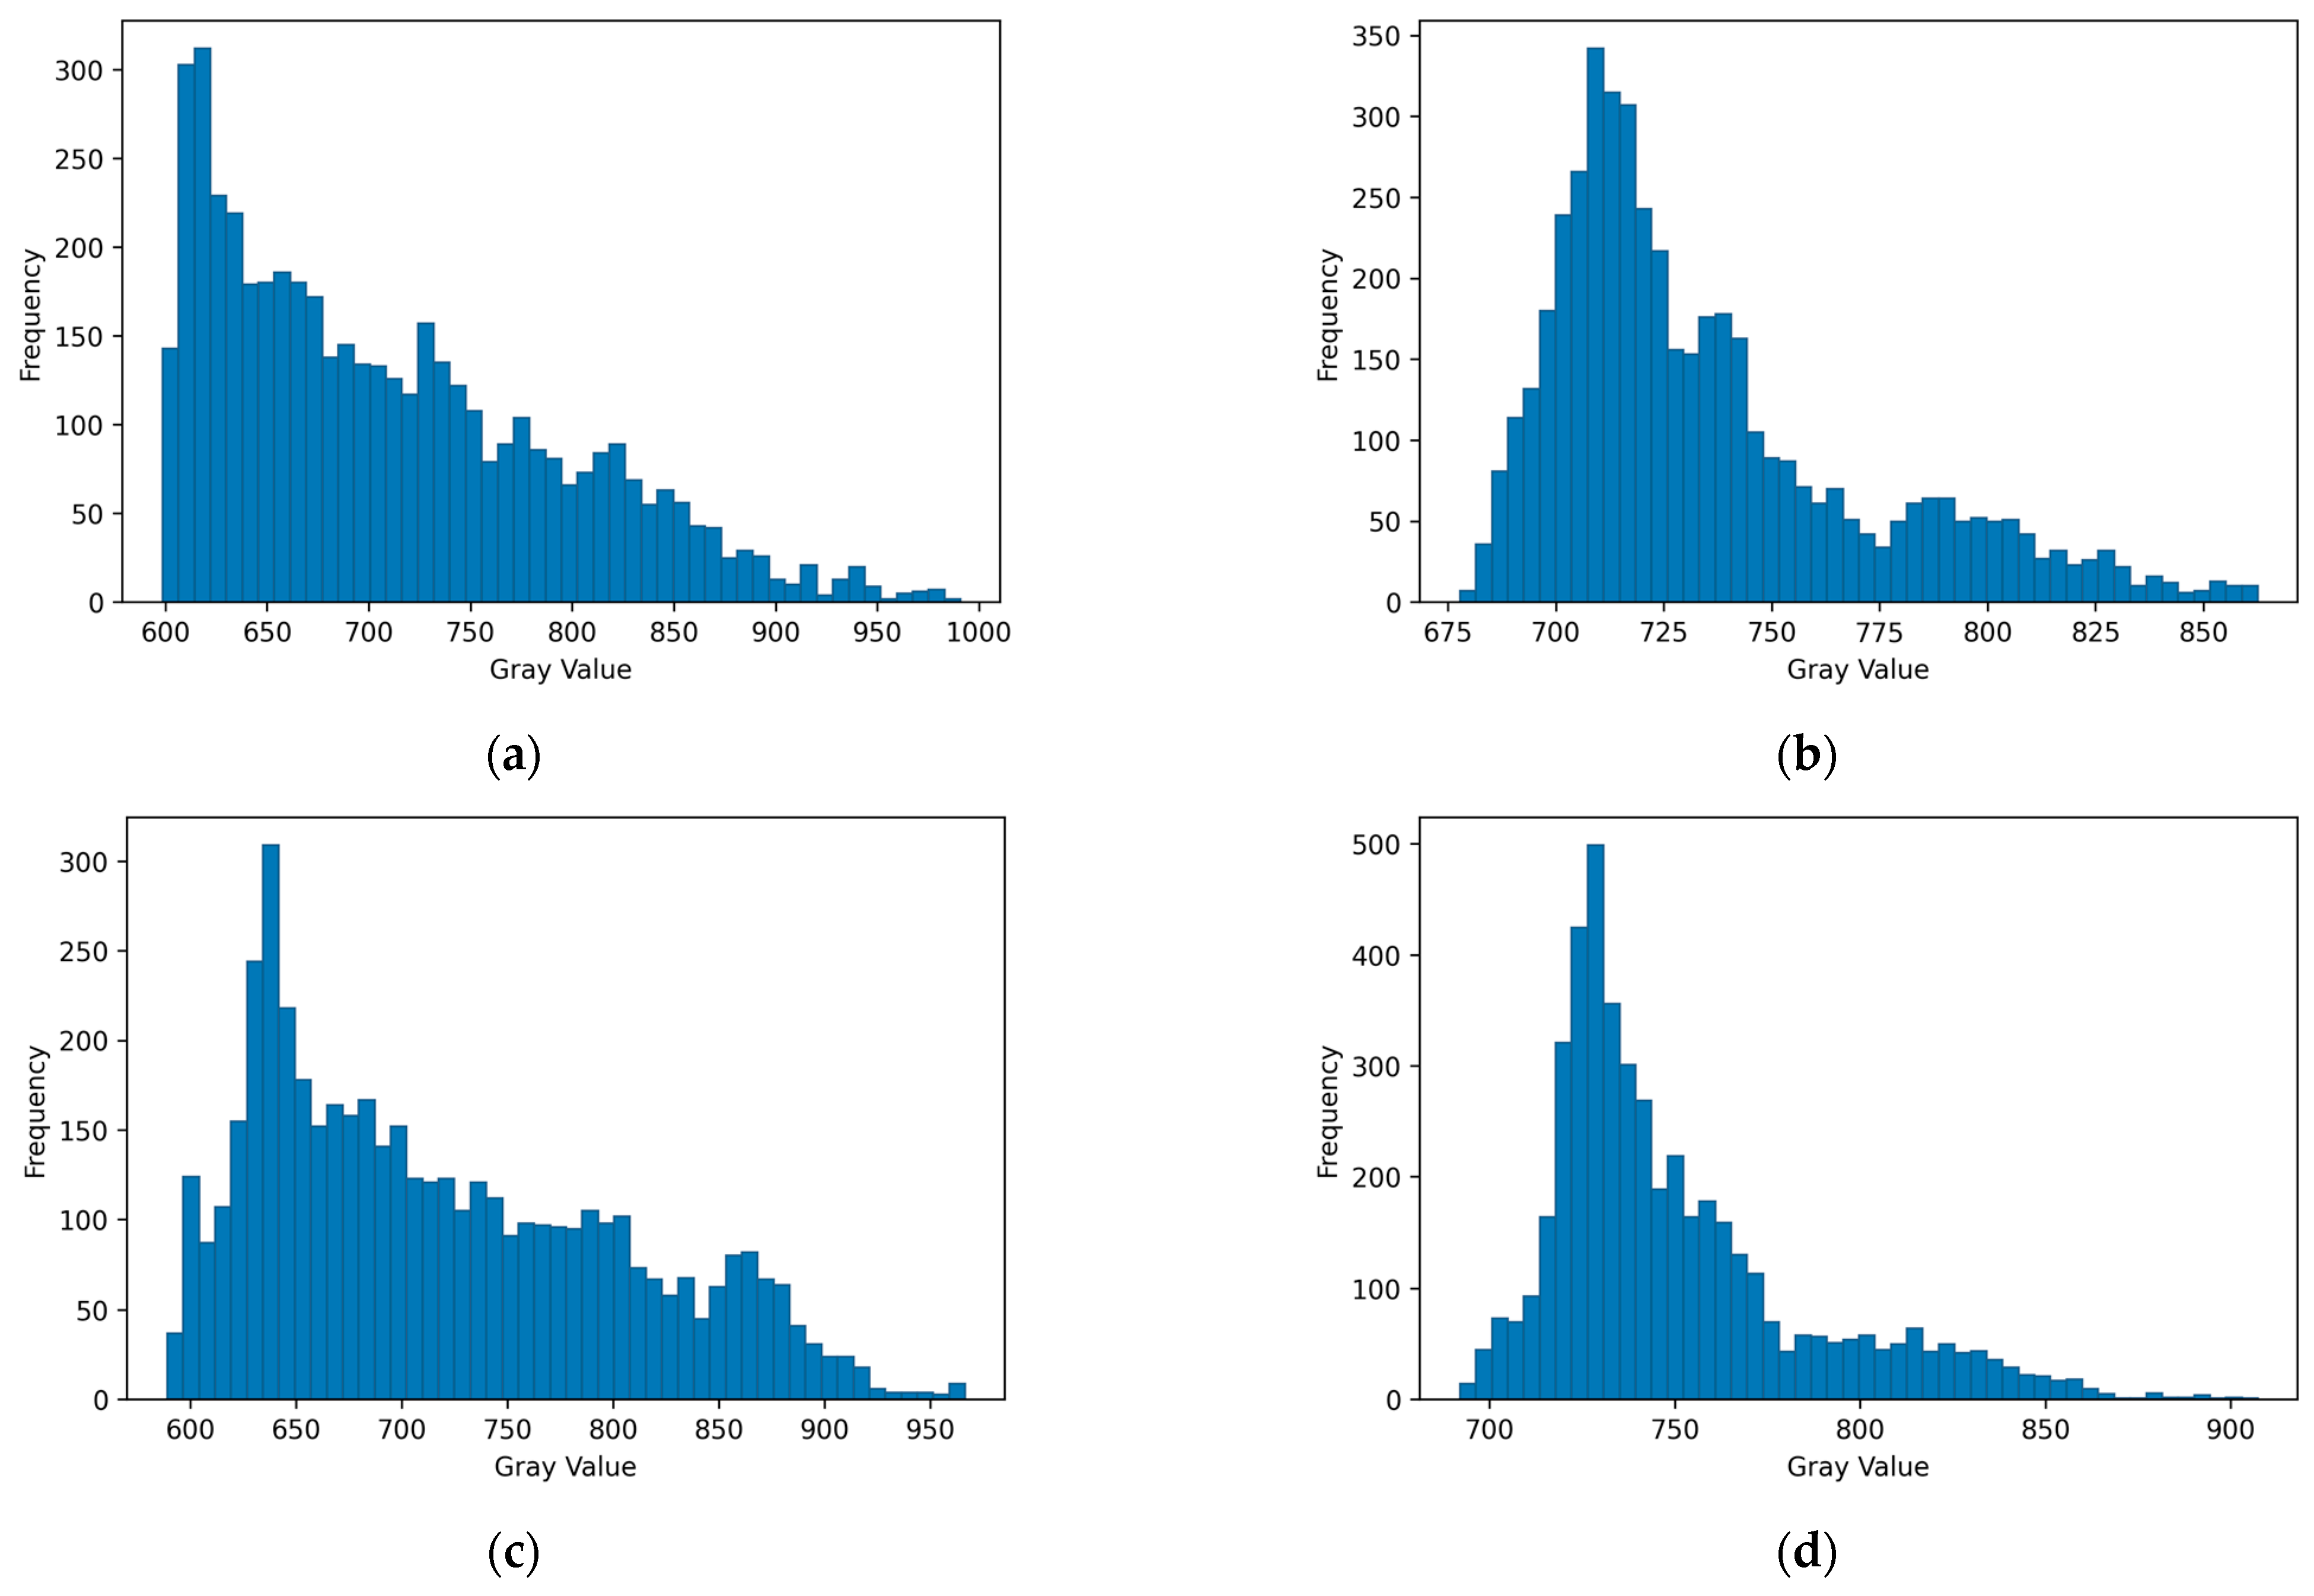
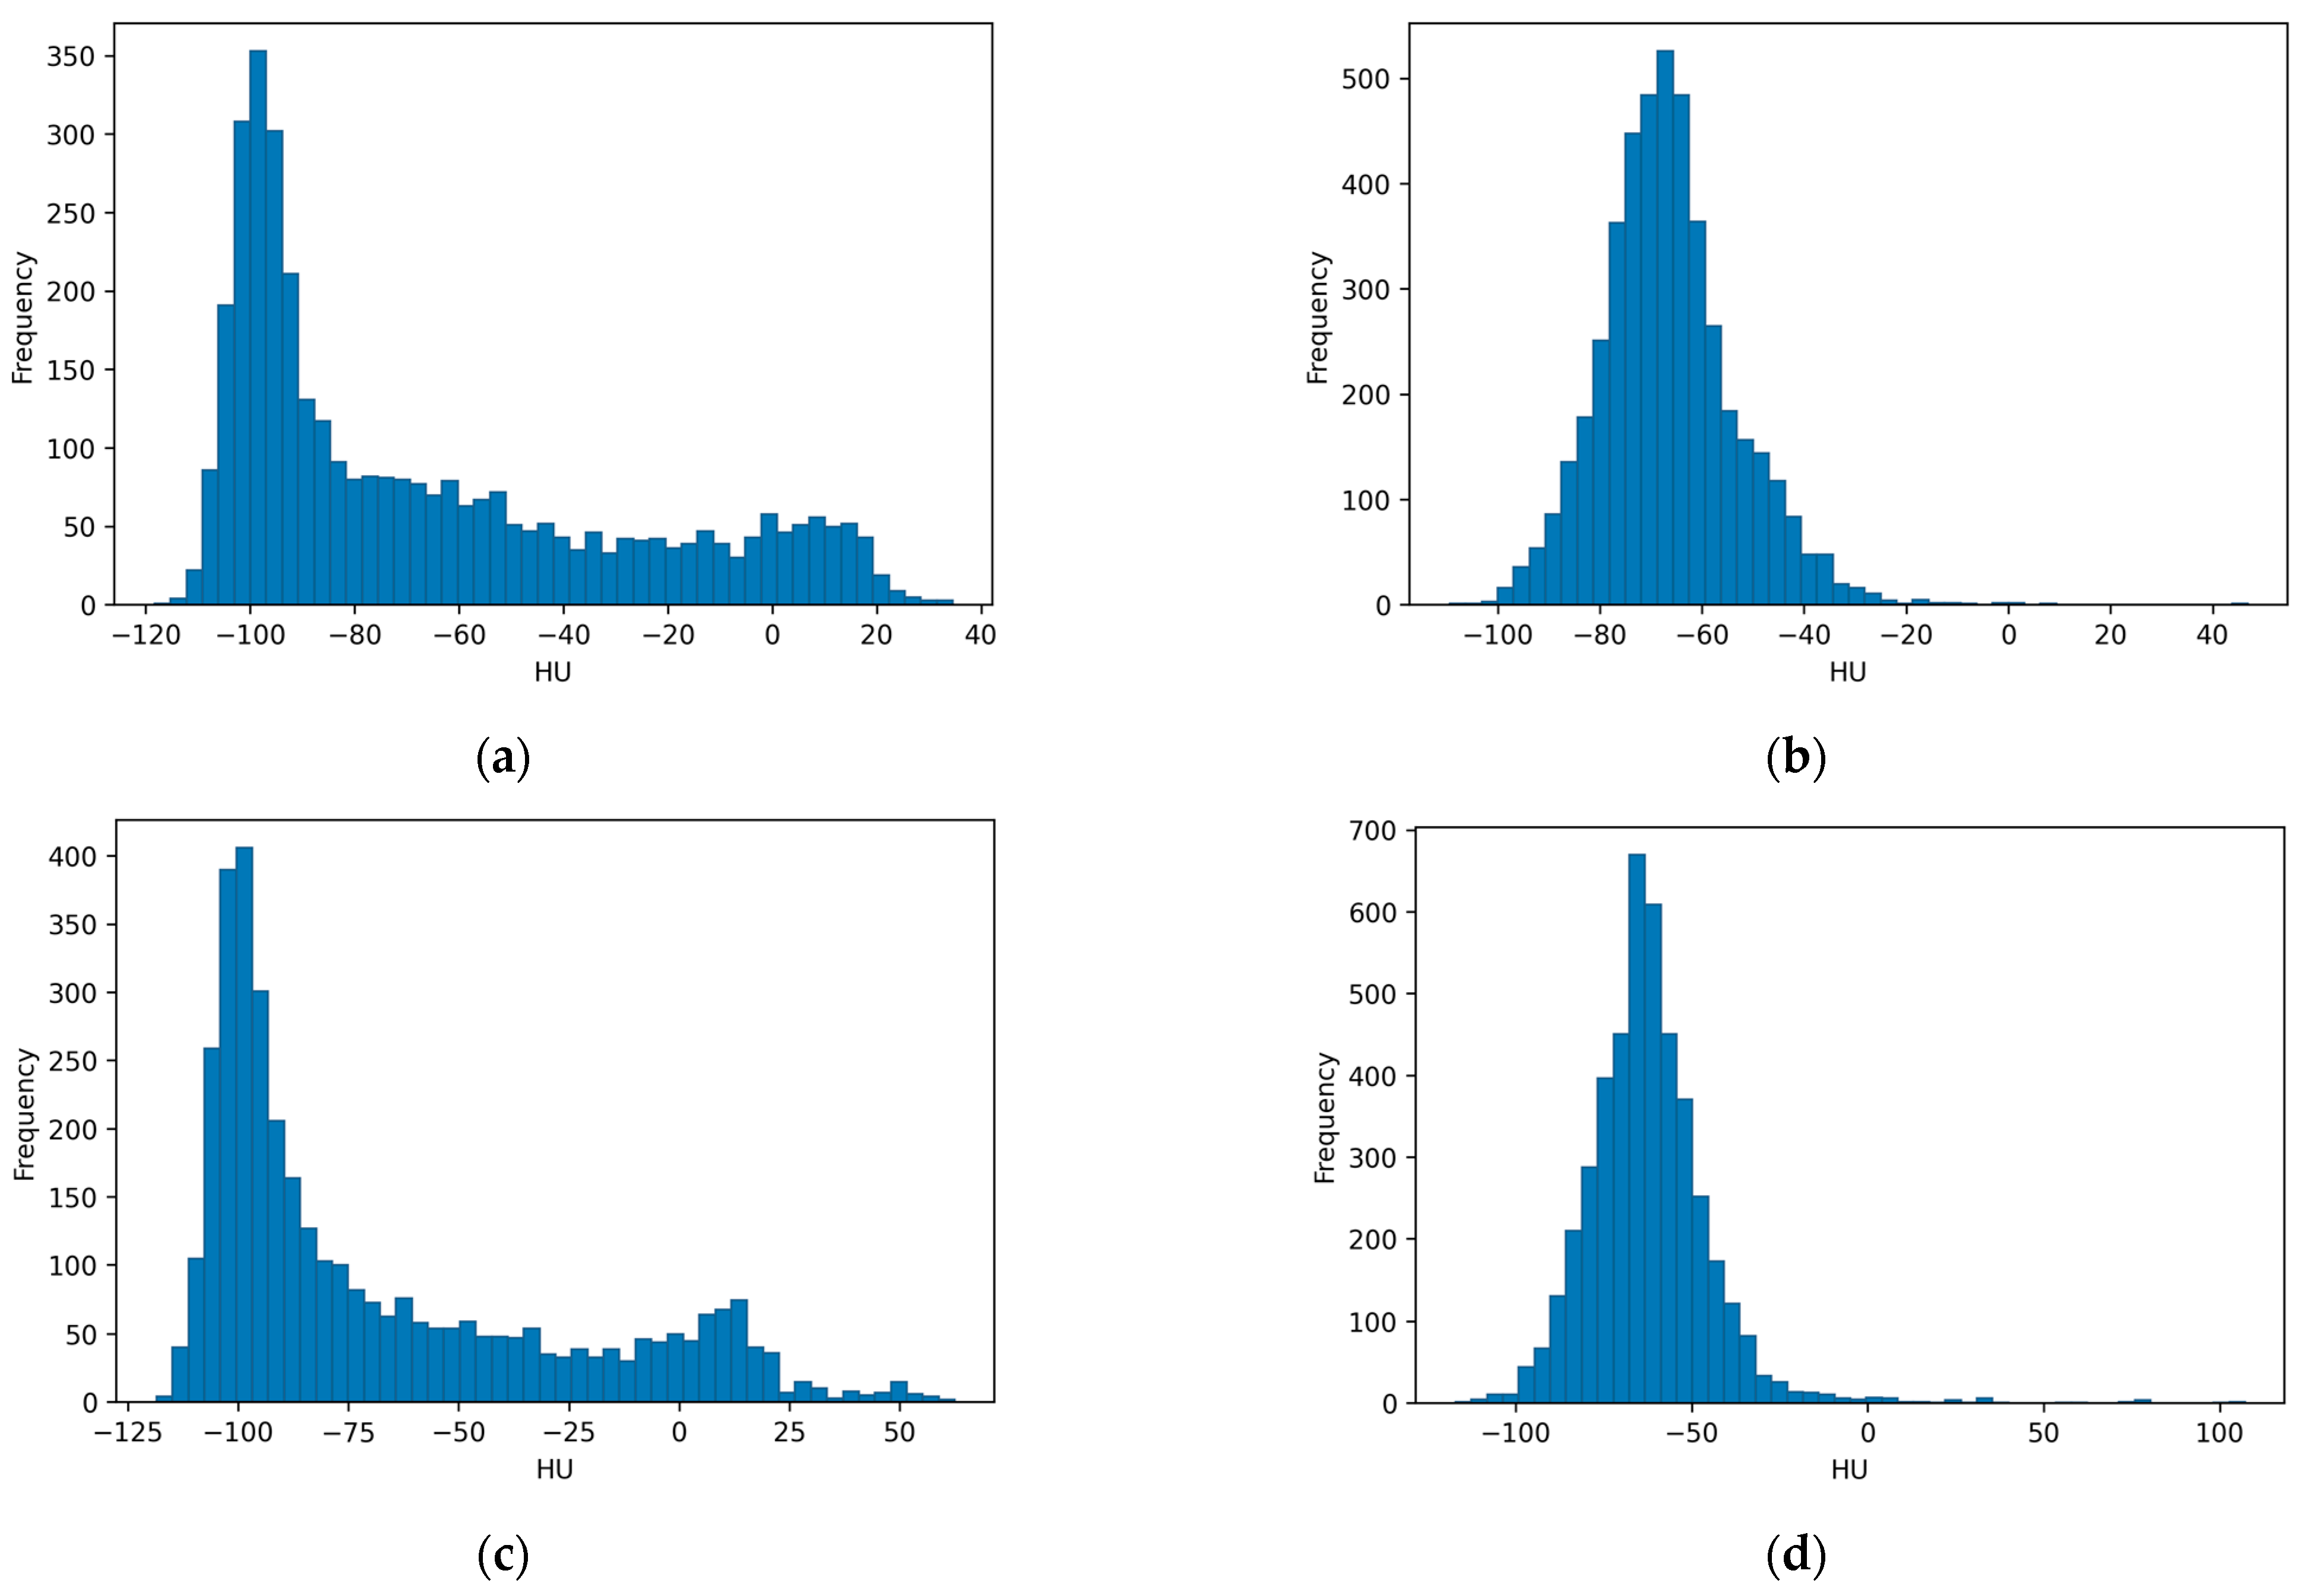
The results from the mean intensity calculations with multiple ROIs with a size of 50 × 50 pixels for the mammography and DBT images and ROIs with a size of 11 × 11 pixels for the CT images are shown as histograms in
Figure 7,
Figure 8 and
Figure 9, respectively. The resulting histograms reveal visual similarity between phantoms BP1 and BP3, which are ASA-HIPS-based and were printed with the Raise3D printer. Likewise, the histograms of the ASA-ABS-based phantoms printed with the Bambu Lab printer—BP2 and BP4—exhibit visual similarities. There are some noticeable variations between the histograms of the two phantom pairs, which may suggest an influence of the STL export procedure.
4. Discussion
This study presents a multimodality evaluation of four 3D-printed breast phantom sections fabricated from the same patient-derived computer model. Two key production parameters were varied: the FFF printing platform with its associated tissue substitute materials and the STL export procedure.
The fabrication approach used two distinct thermoplastic filaments to represent the two dominant breast tissue types—glandular and adipose—within a single FFF print job, showing the most accessible strategy available for producing anthropomorphic phantoms from patient data with consumer-grade equipment. In this study, ASA was assigned to represent glandular tissue and skin across all four phantoms, while the adipose tissue was represented by HIPS in BP1 and BP3 and by ABS in BP2 and BP4. Two capable FFF platforms with dual-material printing capabilities were used, the Raise3D Pro3 Plus with the Hyper Speed upgrade and the Bambu Lab P1S. This dual-material FFF approach to breast phantom fabrication builds on previous work demonstrating the feasibility of filament-based 3D printing for multi-tissue (material) phantom production. Varallo et al. [
9] fabricated fused deposition modeling (FDM)-based compressed breast phantoms derived from patient-based breast CT scans using ABS as a substitute for adipose tissue, together with PLA or PET for glandular tissue. Their study demonstrated that dual-material FDM/FFF phantoms imaged with clinical mammography and DBT systems produced anatomically realistic textures and showed promise for quality assurance and dosimetry applications. The current study extends this approach by evaluating two different tissue substitute combinations: HIPS-ASA and HIPS-ABS. The study of He et al. [
20] emphasized the importance of tissue-equivalent material selection for achieving consistent multimodal phantom performance, which was examined in the current study as well by utilizing the three imaging modalities.
The increased attention to and popularity of 3D printing for radiological phantoms naturally increases the attention paid to the various FFF filament materials and their radiological tissue equivalence. Several systematic studies have examined commercial FFF filaments [
12,
21,
22]. In [
10], ASA was specifically identified as a candidate substitute for glandular breast tissue, while ABS-based materials, together with HIPS, were outlined as candidates for adipose tissue substitutes based on their CT numbers across a range of tube voltages. Both ABS and HIPS were also evaluated by Belarra et al. [
19] as potential substitutes for adipose tissue. The current study examines these two materials and their combination with ASA for the production of inter-tissue contrast across imaging modalities—an investigation not previously performed in this context.
The ASA-HIPS combination (BP1 and BP3) produced better visual and quantitative contrast between the glandular and adipose tissue components than the ASA-ABS combination (BP2 and BP4). In the CT evaluation, all four phantoms exhibited median HU values in the negative range, consistent with low-density soft tissue. However, BP2 and BP4 showed less negative and more tightly distributed HU values compared to BP1 and BP3, indicating closer attenuation properties for the ASA and ABS materials, and consequently reduced tissue contrast. In contrast, HIPS exhibits lower X-ray attenuation than ABS, resulting in a greater attenuation difference relative to ASA and, therefore, improved discrimination between the simulated tissue types. The same trend was observed in mammography and DBT, where BP2 and BP4 produced higher overall gray values but lower tissue contrast than BP1 and BP3.
In the review of anthropomorphic breast phantom development by Glick et al. [
23], the authors emphasize the need for the realistic rendering of tissue contrast. The higher contrast obtained with the ASA-HIPS combination is therefore primarily due to the lower attenuation of HIPS compared with ABS. These observations highlight the importance of selecting phantom materials not only based on their individual attenuation properties but also based on their relative attenuation separation across different X-ray energy ranges. For CT applications, both material combinations produced mean HU values that correctly reflected the HUs in real patients’ CT images. For the mammographic energy range, reference data have been reported by Delogu et al. [
24]; however, their study was based on analytical simulations using a simplified cylindrical breast phantom. Therefore, these data are not directly comparable with the present anthropomorphic, patient-derived phantoms imaged on a clinical system.
Furthermore, Homolka et al. [
25] noted the challenge with commercially available 3D printing materials, which are optimized for mechanical performance and not for radiological tissue equivalence, and the lack of availability of such materials remains a constraint in phantom production. Therefore, phantom design efforts should include multi-material contrast characterization and combinational suitability as well, rather than evaluating candidate materials in isolation.
However, in the multi-material FFF printing of complex anatomical objects such as breast phantoms, the digital model must be decomposed into separate STL files for each tissue type, which are then combined in the slicing software and assigned to different extruders/materials. The algorithm used to generate the STL mesh from the volumetric image data determines the geometric accuracy and specifically the quality of the shared boundary between adjacent tissue volumes.
A common approach used in STL export tools is to generate the mesh using isosurface algorithms such as Marching Cubes, which approximate curved and irregular surfaces as tessellations of triangular faces [
26]. The isosurface representation of each tissue is computed independently, and the resulting meshes do not perfectly interlock at the shared interface. As demonstrated in the current study, as well as in other investigations [
16,
27], this can lead to the formation of unwanted cavities and gaps in the combined multi-material object. This type of artifact is visible in the image of BP2 (
Figure 3b), where the adipose (white ABS) and glandular structures (gray ASA) on the surface layer meet. In contrast, the firm, gap-free interfaces achieved with the in-house STL export procedure can be seen in BP3 (
Figure 3a). The procedure addresses this problem by generating a prismatic representation of the tissue boundaries while preserving the original voxel geometry [
16]. Rather than fitting smooth triangulated surfaces to the segmented volumes, the script preserves the shapes of the individual voxels at the interface, creating a stepped but geometrically exact boundary that fully closes the gap between adjacent volumes. This results in a continuous interface with no cavities and indentations. However, previous investigations [
16,
27] showed that the indentations from the standard export procedure are mainly confined and prominent in the top and bottom layers, which explains why the bulk radiological metrics, such as the HU values and gray value distributions measured within the ROIs, do not show a strong systematic difference between STL procedures.
Nevertheless, for applications where the phantom surface or the structural integrity of the printed object matters, or any application where the phantom is physically sectioned, the in-house-developed STL export procedure will produce substantially superior results. Kamio et al. [
28] demonstrated that different STL export software packages produce measurably different model geometries from the same DICOM input data, with shape differences correlated with algorithmic choices in segmentation and mesh generation. They concluded that the quality of the 3D-printed model is directly related to the quality of the STL data.
Furthermore, Fogarasi et al. [
29] categorized the geometric variability in image-to-model transformation into segmentation and editing errors and noted that smoothing and mesh refinement can reduce staircase artifacts but may also inadvertently alter anatomical geometries. The in-house STL export procedure (EP2) accepts the staircase appearance of voxel boundaries as a geometric trade-off in exchange for eliminating the interface gap problem. Future work could explore hybrid approaches that combine the benefits of both approaches. Juergensen et al. [
30] further demonstrated that STL files can contain artifacts, mesh gaps, and vector misalignment and that digital editing is crucial for printing quality. The presented in-house procedure (EP2) addresses this issue through an automated solution that avoids manual mesh adjustments.
Some notable limitations of the present study should be acknowledged. The printer and material variables were confounded by design. The Raise3D Pro3 Plus was used with ASA-HIPS and the Bambu Lab P1S with ASA-ABS, meaning that the observed differences between the phantom groups cannot be attributed exclusively to the material or printer selection. The two platforms differ in their dual-material handling architectures. The Raise3D Pro3 Plus utilizes two printing heads, each dedicated to a specific printing material, while the Bambu Lab P1S uses a single printing head with Automatic Material System (AMS) material switching. Although both are high-end commercial FFF printers, differences in kinematics, thermal management, and motion system design remain important for part quality, even among such 3D printers [
31]. However, such platform differences are expected to be secondary to the effects of material selection on radiological fidelity, since the observed contrast differences are more plausibly explained by the substantially different attenuation properties of HIPS and ABS than by mechanical differences between the two printers. A fully crossed printer–material design was beyond the scope of the present study; however, in a future study, such an approach would allow the contributions of the printer hardware and material selection to be formally separated.
Further limitations concern the tissue substitute materials’ attenuation properties. Material selection in the present study relied on characterization across CT tube voltages. A material’s relative attenuation to tissue is energy-dependent, and equivalence at CT energies does not guarantee equivalent behavior under the lower-energy spectra used in mammography. The reported values for the Weber contrast, CNR, and SNR reflect the empirical performance of the phantoms on the imaging systems used, not independent spectral verification. The dedicated characterization of the specific materials and combinations using the mammography system is planned as the next stage of this work.




 ,