


Abstract
Artificial intelligence applications in histopathological diagnostics are rapidly expanding, with particular promise in complex hematological malignancies where diagnostic accuracy remains challenging and subjective. This study undertakes a scoping review to systematically map the extent of research on artificial intelligence applications in histopathological diagnostics of leukemias, examine geographic distribution and methodological approaches, and assess the current state of AI model performance and clinical readiness. A comprehensive search was conducted in the Scopus database covering publications from 2018 to 2025 (as of 12 July 2025), using five targeted search strategies combining AI, histopathology, and leukemia-related terms. Following a three-stage screening protocol, 418 publications were selected from an initial pool of over 75,000 records across multiple countries and research domains. The analysis revealed a marked increase in research output, peaking in 2024 with substantial contributions from India (26.3%), China (17.9%), USA (13.8%), and Saudi Arabia (11.1%). Among 43 documented datasets ranging from 80 to 42,386 images, studies predominantly utilized convolutional neural networks and deep learning approaches. AI models demonstrated high diagnostic accuracy, with 25 end-to-end models achieving an average accuracy of 97.72% compared to 96.34% for 20 classical machine learning approaches. Most studies focused on acute lymphoblastic leukemia detection and subtype classification using blood smear and bone marrow specimens. Despite promising diagnostic performance, significant gaps remain in clinical translation, standardization, and regulatory approval, with none of the reviewed AI systems currently FDA-approved for routine leukemia diagnostics. Future research should prioritize clinical validation studies, standardized datasets, and integration with existing diagnostic workflows to realize the potential of AI in hematopathological practice.
1. Introduction
Today, an increasing emphasis on deep learning algorithms permeates all domains of human activity. In medicine, AI-based decision aids are also gaining importance. The field in which computers could be an invaluable help for clinicians is the diagnosis of leukemias. Leukemias were among the 15 most common neoplastic diseases and in the top 10 when it comes to mortality in 2024 according to the WHO [1]. At the same time they are the most common neoplasms in the Polish pediatric population, accounting for 28.7% of child tumors [2]. In 2024, in the USA, 62,000 new leukemia cases were expected to be diagnosed, one-third of which will die [3]. During the last 30 years, a constant increase in cases has been observed (although with regional differences) [4]. Every diagnosis of leukemia must be confirmed by a pathologist with a microscope. Currently, ever more histological and cytological slides are scanned by specialized scanners and then stored digitally. This scoping review explores the application of this technology in leukemia diagnostics; it summarises and compares existing models and the data sets on which they are built. Given the rapidly expanding and methodologically diverse field of AI applications in histopathological diagnostics of leukemias, a scoping review methodology was chosen to map the breadth of literature, identify key concepts, and examine research trends. This approach is particularly suited for emerging fields where studies employ heterogeneous methodologies and the primary goal is to provide a comprehensive overview rather than answer a specific clinical question. The inclusion of bibliometric analysis further reinforces this choice, as it complements the exploratory objectives of scoping reviews by identifying geographic patterns and temporal trends in research activity. The review describes biases, challenges, and limitations that may hinder the spread of AI use in leukemia diagnostics and examines the possible effects of their action on the final results of the diagnostic process.
2. Leukemias and Their Diagnostic Process
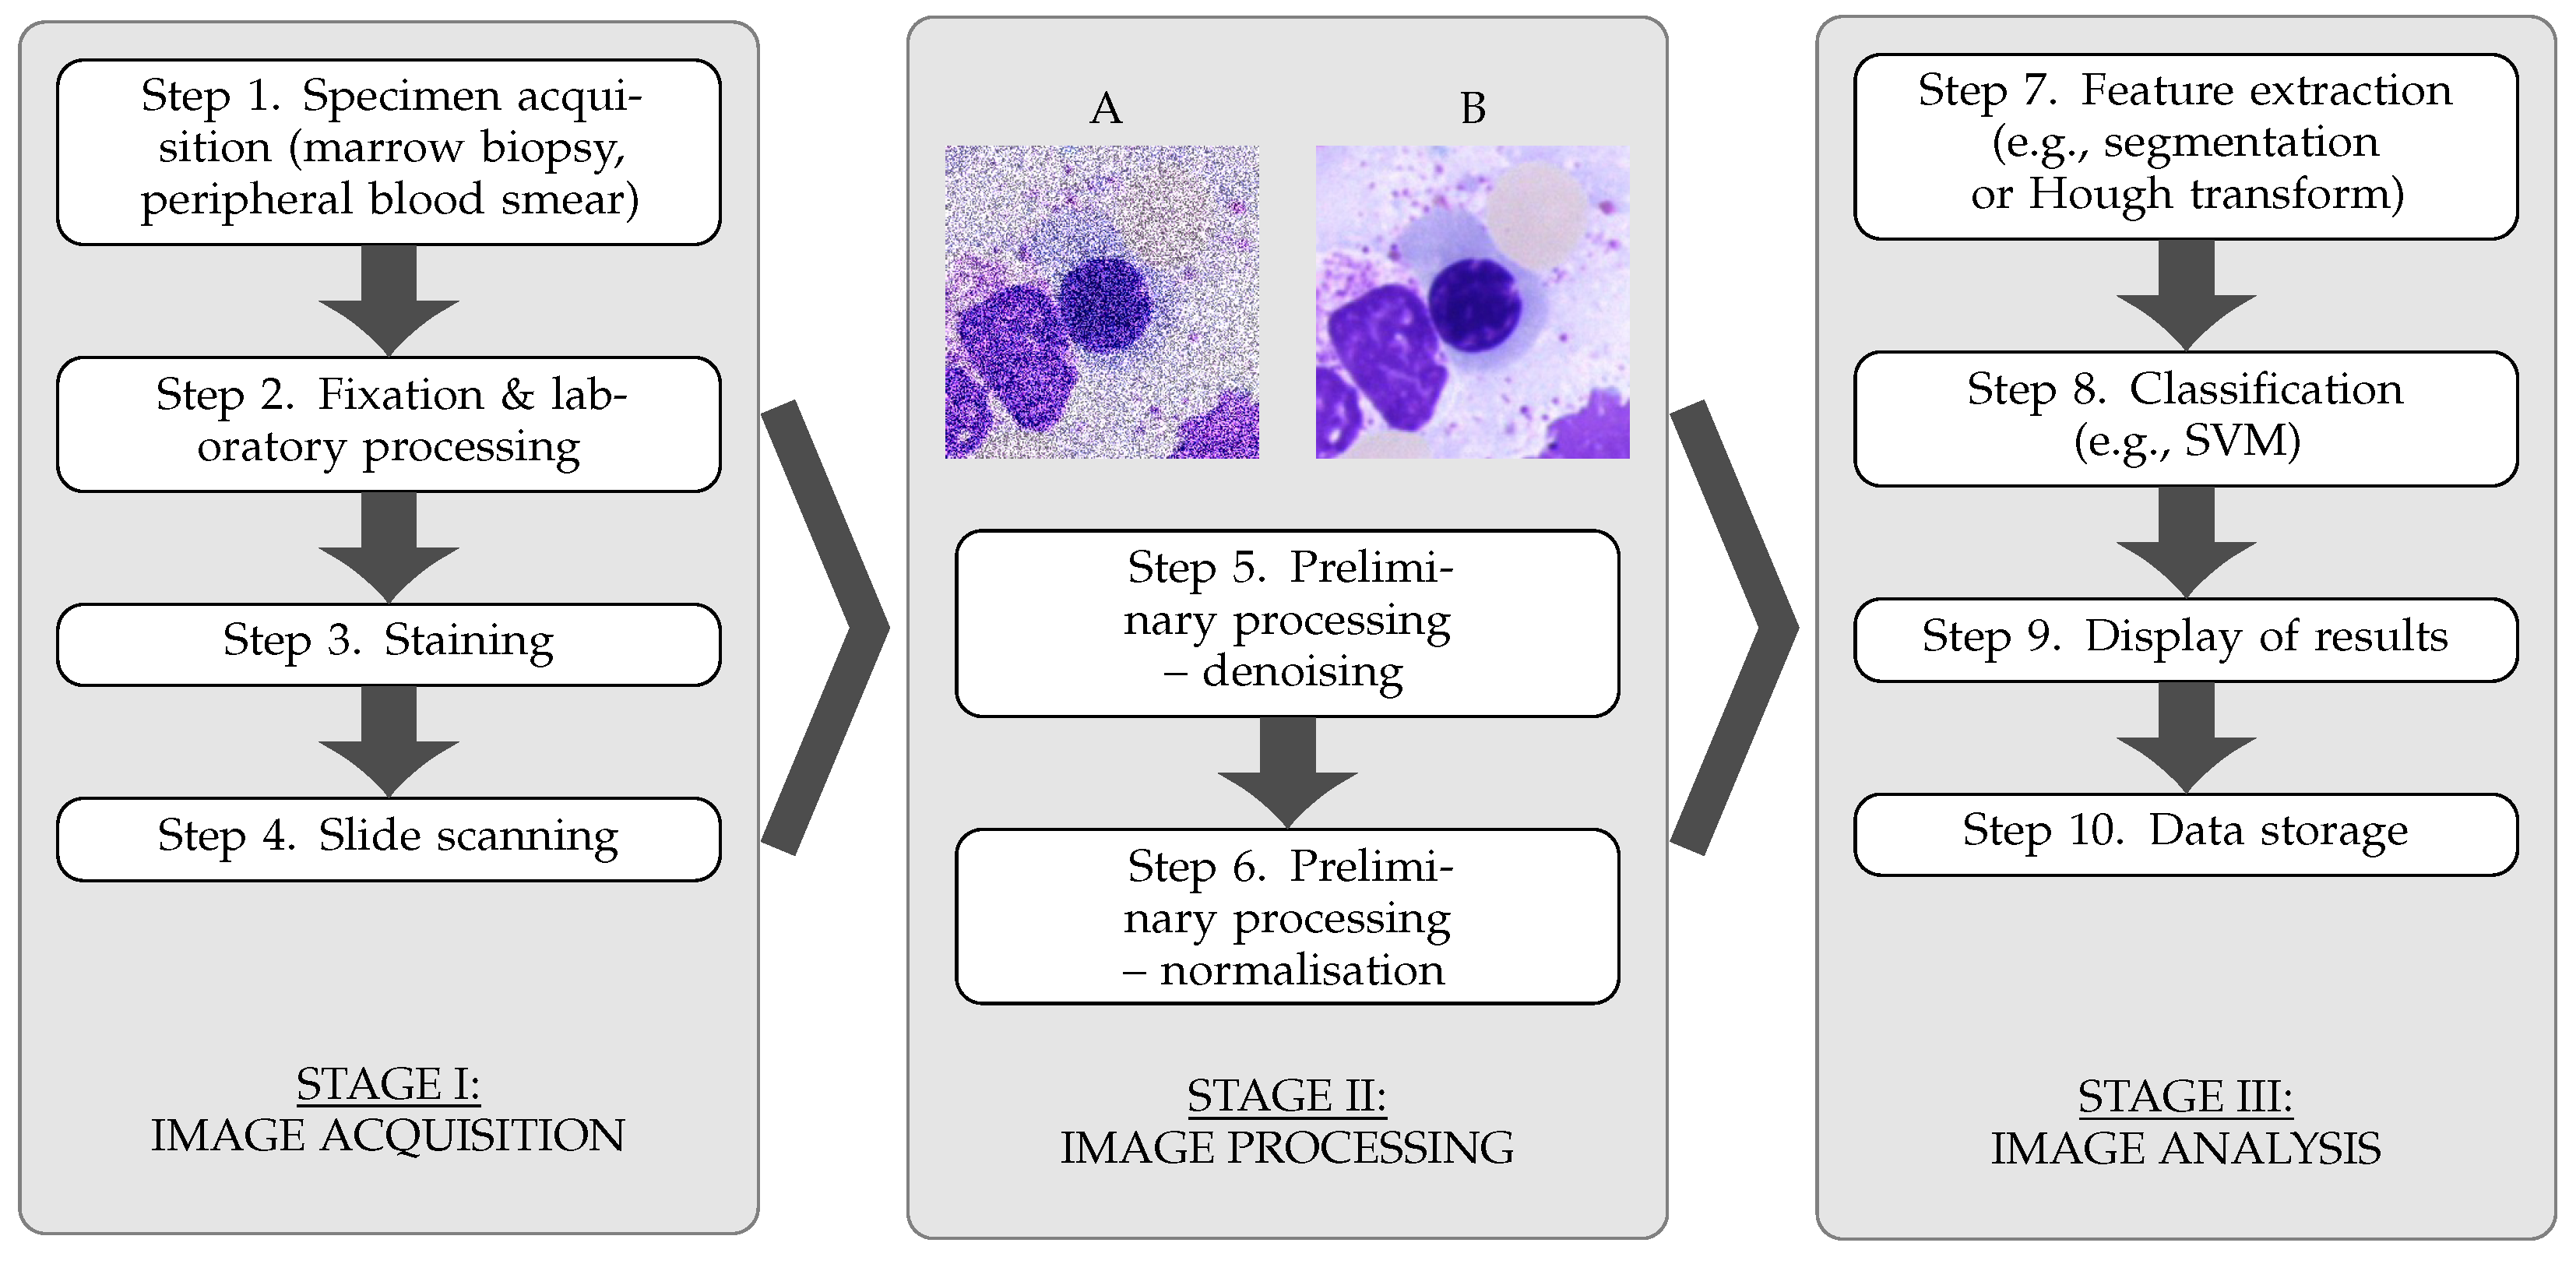
Hematopoiesis (the process in which cellular elements of human blood are created) in humans is very complex. While a detailed analysis and description of all stages and forms of cell development is outside the scope of this review, one has to note that normally, only final stages are represented in blood and intermediate forms are stored within the bone marrow [5]. The next paragraphs help to build an understanding of the diagnostic process of leukemia and the complexities one has to understand to accomplish it. Leukemia is a neoplasm that derives from white blood hematopoietic cells and is caused by uncontrolled growth of one intermediate form in the hematopoietic chain. Rarely, it can be a normal, functional cell, which due to mutation grows uncontrollably. An example of such leukemia can be leukemia introduced by HTLV-1 [6]. Such cells are not functioning properly and their growth causes suppression of other proper cells in blood. This leads to various symptoms, ranging from frequent infections to coagulation disorders. If untreated, symptoms may lead to the death of the patient. General symptomatology of oncological disease (e.g., fatigue, weight loss) is often associated. Medical practitioners divide leukemias into four main types, depending on the cells that are overgrowing and on the rate of growth and disease dynamics: lymphoblastic leukemias (acute—ALL or chronic—CLL) and myeloid leukemias (acute—AML or chronic—CML) [7]. This classification is a simplification, since some leukemias are elusive and cannot be clearly ascribed to one type. There are many rare types of leukemia too, including hairy-cell leukemia (HCL) [8], prolymphocytic leukemia (PLL) [9], or large granular lymphocytic leukemia (LGLL) [10]. It is also possible for a mixed-phenotype leukemia to occur, where myeloid and lymphoid features are combined [11]. In order to be qualified as a type, leukemia must have a certain percentage of cancerous cells (e.g., >20% blasts in AML) or have defined cytogenetic abnormalities. If abnormalities occur, then the percentage of cells we have to establish the diagnosis of leukemia can either be too small or not significant enough for diagnosis. The aforementioned main types are further divided into subtypes, e.g., according to the French-American-British (FAB) classification [12] (acute myeloid leukemia into subtypes M0–M7, or acute lymphoblastic leukemia into subtypes L1–L3). The identification of the main type of leukemia is often insufficient and doctors need to know which exact subtype they are to treat. The therapy differs between leukemia types and subtypes, with some of them more threatening than others, mandating urgent response from the clinicians—a standard example of such subtype is acute promyelocytic leukemia (M3 subtype of AML according to FAB classification, where promyelocytes are the neoplastic cells), which causes life-threatening coagulation disorders (DIC) [13]. On the other hand, many chronic leukemias are indolent, and sometimes patients do not experience any symptoms for a long time. A good example of such leukemia is CLL, often diagnosed only after accidental discovery of lymphocytosis in patients’ blood [14]. A brief overview of leukemias, their markers and their diagnostic criteria are summarized in Table 1. Additionally, We present the stages of diagnostics using AI in Figure 1.
Table 1.
Overview of basic leukemia types *.
Figure 1.
Stages of diagnostic process of leukemias using AI. Photos A and B were taken from Matek, C., Krappe, S., Münzenmayer, C., Haferlach, T., & Marr, C. (2021) [26]. An Expert-Annotated Dataset of Bone Marrow Cytology in Hematologic Malignancies [Data set]. The Cancer Imaging Archive. https://doi.org/10.7937/TCIA.AXH3-T579, licensed under CC BY 4.0. Available at: https://creativecommons.org/licenses/by/4.0.
The diagnosis of leukemia can only be made by histopathological or cytopathological examination. Whereas histopathology is occupied with tissue samples, cytopathology analyses smears, where the intercellular structure is lost, and the cells are separated from each other. Both approaches provide important information and contribute to the final diagnosis [27]. Of course, the diagnosis of leukemia cannot be based solely on the morphological characteristics of cells under the microscope. Flow cytometry, immunohistochemical methods, and analysis of cell genotypes are used to support diagnosis [28]. Without them it would neither be possible to diagnose nor to treat leukemia. However, all these methods come after the morphological analysis, and the diagnostic process starts with histo- and cytology. The key step of this diagnostic process is also the one prone to most significant errors. The analysis of microscopic slides is done by eye and depends on the experience, expertise, and perceptivity of the analyst. The risk of errors is then high and unpredictable and can reach 40% while differentiating between leukemia subtypes [29]. This fact does not imply that the diagnosis of the leukemia subtype is based solely on microscopy without employing other techniques that diminish the risk or error, but rather shows how subjective and difficult image analysis can be. While there is no diagnostic problem if, e.g., there are 70% or 50% of blasts in an AML specimen (we need 20% to be allowed to diagnose it), trouble begins if the amount is close to 20%—we cannot with certainty say if there are 19% or 21% of blasts. This is a field where an AI model trained to recognize leukemia cells, with its training and visual recognition capabilities far better than human, will immensely facilitate diagnostics.
3. Bibliometric Analysis
In order to evaluate the current research trends and scientific interest in the application of artificial intelligence (AI) in histopathological diagnostics of leukemias, a bibliometric analysis was performed.
3.1. Methodology
This scoping review was conducted and reported in accordance with the PRISMA Extension for Scoping Reviews (PRISMA-ScR) guidelines (Supplementary Materials). No review protocol was registered for this scoping review, as protocol registration is not mandatory for scoping reviews, unlike systematic reviews, which require PROSPERO registration.
Data source: Scopus
Time frame: 2018–2025 (as of 12 July 2025)
Keywords/Queries:
- Q1: (“artificial intelligence” OR “AI” OR “machine learning” OR “deep learning”) AND (“histopathology” OR “digital pathology” OR “histological image” OR “microscopic image”) AND (“diagnosis” OR “diagnostic support” OR “classification”)Broad general query covering applications of artificial intelligence in histopathological and cytological image analysis in hematology, without limiting to specific leukemia types.
- Q2: (“artificial intelligence” OR “AI” OR “deep learning” OR “machine learning”) AND (“leukemia” OR “leukaemia” OR “AML” OR “ALL” OR “CML” OR “CLL”) AND (“diagnosis” OR “diagnostic aid” OR “detection” OR “classification”) AND (“histopathology” OR “cytology” OR “microscopic image” OR “blood smear” OR “bone marrow smear”)A more specific query targeting the use of machine learning and deep learning methods in leukemia diagnostics based on microscopic images, particularly focusing on blood and bone marrow cell morphology.
- Q3: (“convolutional neural network” OR “CNN” OR “deep learning”) AND (“blood smear” OR “bone marrow smear” OR “cytological image” OR “histopathology”) AND (“leukemia” OR “blood cancer” OR “hematological malignancy”)Query focusing on AI applications in automatic classification and detection of hematological diseases, with an emphasis on computer-aided diagnostic systems.
- Q4: (“artificial intelligence” OR “machine learning”) AND (“leukemia subtype” OR “ALL subtypes” OR “AML subtypes” OR “FAB classification” OR “immunophenotyping”) AND (“classification” OR “differentiation” OR “subtype detection”)Query focused on systematic reviews, meta-analyses, and review articles on the role of AI in leukemia diagnostics, capturing trends and current knowledge summaries.
- Q5: (“machine learning” OR “deep learning”) AND (“SVM” OR “support vector machine” OR “random forest” OR “CNN” OR “neural network”) AND (“leukemia” OR “hematological malignancy”) AND (“image analysis” OR “cell classification”)Technical query covering innovative algorithms, neural network architectures (e.g., CNN), and explainable AI systems in morphological image analysis for hematologic diagnostics.
Inclusion criteria:
- Language: English
- Publication types: Articles, Reviews
- Topic: AI in histopathological/cytological diagnostics of leukemias
Screening protocol:
Three-stage abstract and title selection:
- From each publication set, we selected papers whose abstracts/titles contained at least one keyword from the:
- AI group (“artificial intelligence”, “ai”, “machine learning”, “deep learning”, “neural network”, “cnn”, “convolutional neural network”, “computer-aided diagnosis”, “automated diagnosis”, “intelligent system”).
- Morphological image analysis group (“histopathology”, “histopathological”, “cytology”, “cytological”, “microscopic image”, “blood smear”, “bone marrow”, “digital pathology”, “cell morphology”, “image analysis”).
- From the publications passing the previous screening, we additionally selected only those where the abstracts/titles contained the word “leukemia”.
- Abstracts and titles of the selected publications were then analyzed, and those outside our thematic scope were excluded.
Deduplication: duplicate removal based on titles.
Data extraction and charting:
Data extraction was performed by authors using a standardized approach to capture key variables from included publications. For each study, the following information was systematically extracted: publication details (year, citations), dataset characteristics (size, resolution, magnification, material type), diagnostic focus (leukemia type, classification task), methodological approach (segmentation method, classifier type), and performance metrics (accuracy, sensitivity, specificity). The extracted data were organized into structured tables to enable systematic comparison and analysis of AI models and datasets used in leukemia diagnostics (see tables from Section 4 and Section 5) to enable systematic comparison and analysis of AI models and datasets used in leukemia diagnostics.
Critical appraisal was not performed as it is not typically required for scoping reviews focused on mapping literature and identifying research trends rather than evaluating evidence quality.
3.2. Results
The queries formulated and used in the Scopus database were characterized by high sensitivity but very low specificity. Designing more selective and complex queries carried the risk of omitting publications relevant to the topic of this study. As a result, thousands of publications were initially retrieved. From these, through the application of the triple-stage screening algorithm described earlier, several hundred articles were ultimately selected that reflect the scientific community’s interest in the subject of this review. While compiling the analysis, we took into consideration only such systems of artificial intelligence that work on images and carry out image analysis. We left outside the scope of our work models that analyze specific genetic mutations or chemical biomarkers and focused only on systems that analyze cellular morphology based on microscopic slides. The results of the analysis for each query are summarized as follows:
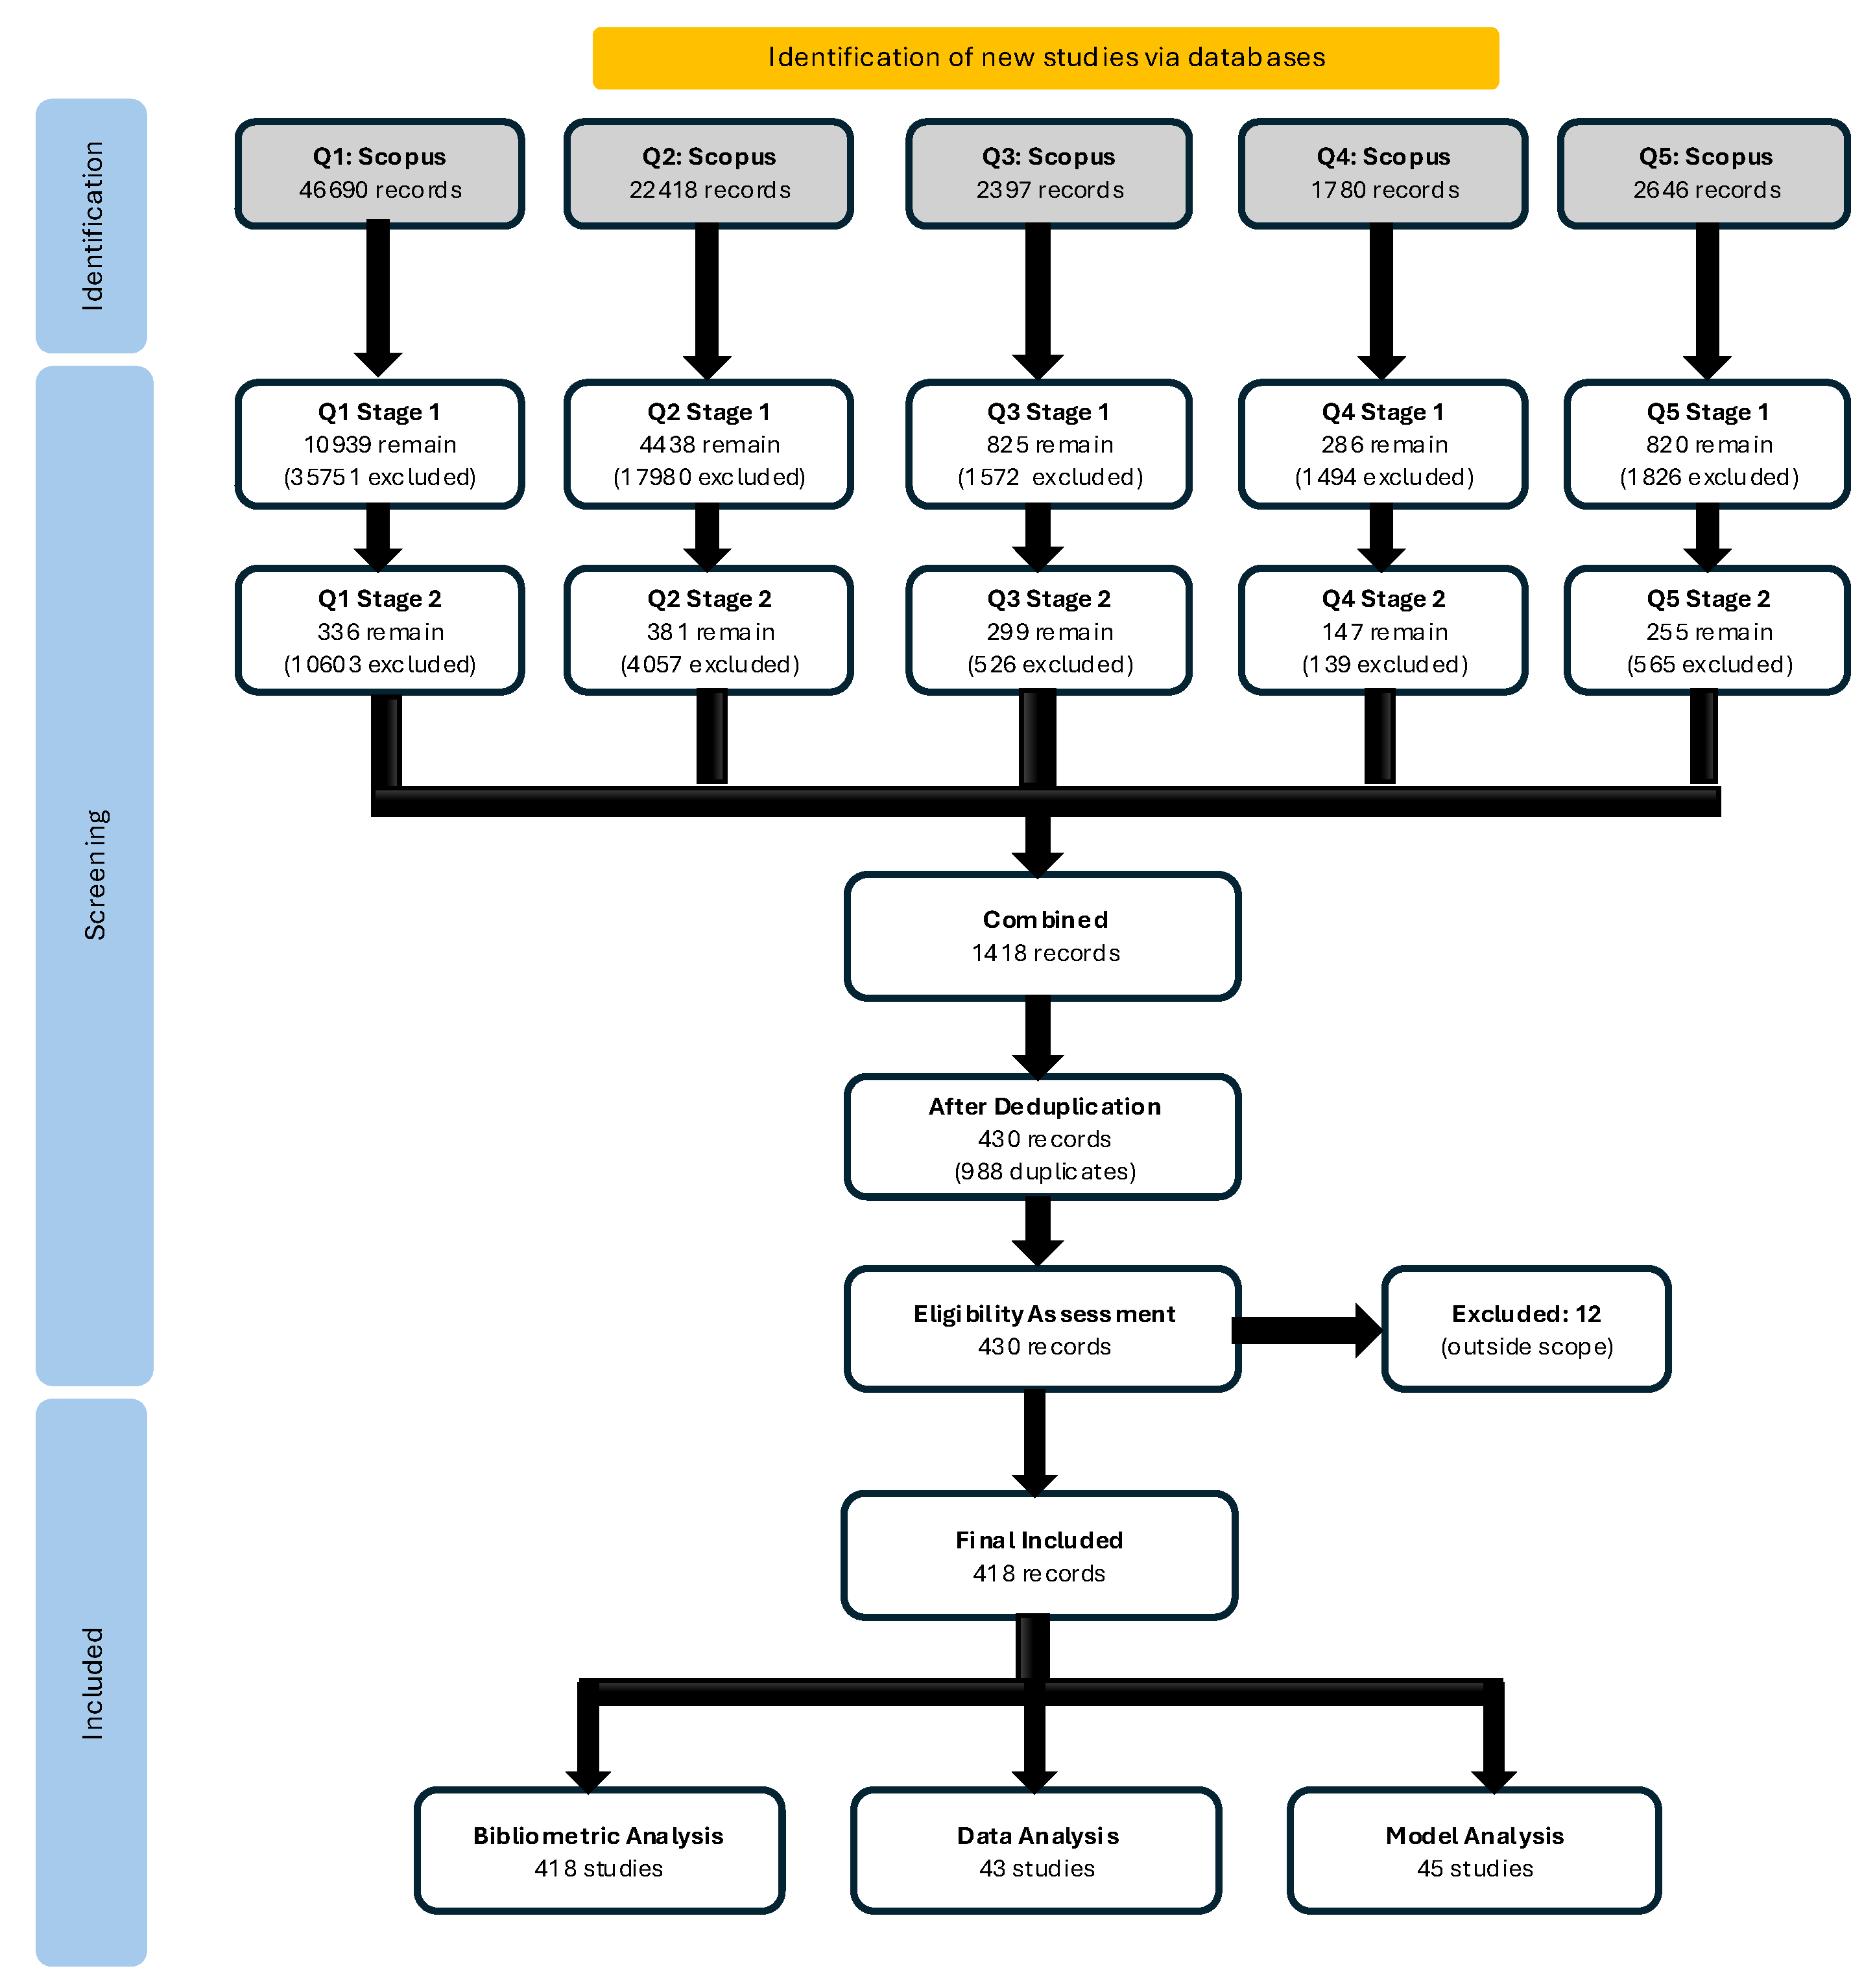
- Q1: 46,690 publications retrieved from Scopus → 10,939 after the first selection stage → 336 after the second selection stage.
- Q2: 22,418 publications retrieved from Scopus → 4438 after the first selection stage → 381 after the second selection stage.
- Q3: 2397 publications retrieved from Scopus → 825 after the first selection stage → 299 after the second selection stage.
- Q4: 1780 publications retrieved from Scopus → 286 after the first selection stage → 147 after the second selection stage.
- Q5: 2646 publications retrieved from Scopus → 820 after the first selection stage → 255 after the second selection stage.
After combining the publications from all queries and removing duplicates, a total of 430 articles were obtained. Following a detailed analysis of abstracts and titles, 12 articles were excluded as they were outside the scope of interest. For the complete PRISMA flow diagram, please refer to Figure A10. This three-stage analysis enabled reliable filtering of several tens of thousands of publications, ultimately achieving a retention rate of 97.2%. However, this figure does not reflect the actual sensitivity, as the number of relevant articles potentially lost at the query stage remains unknown.
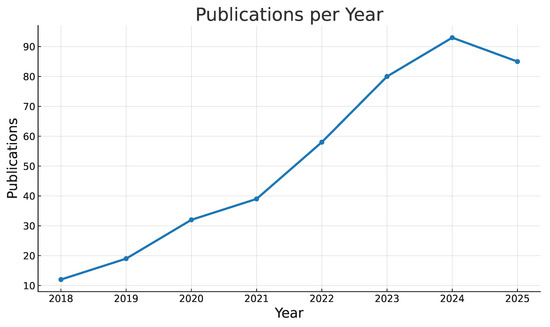
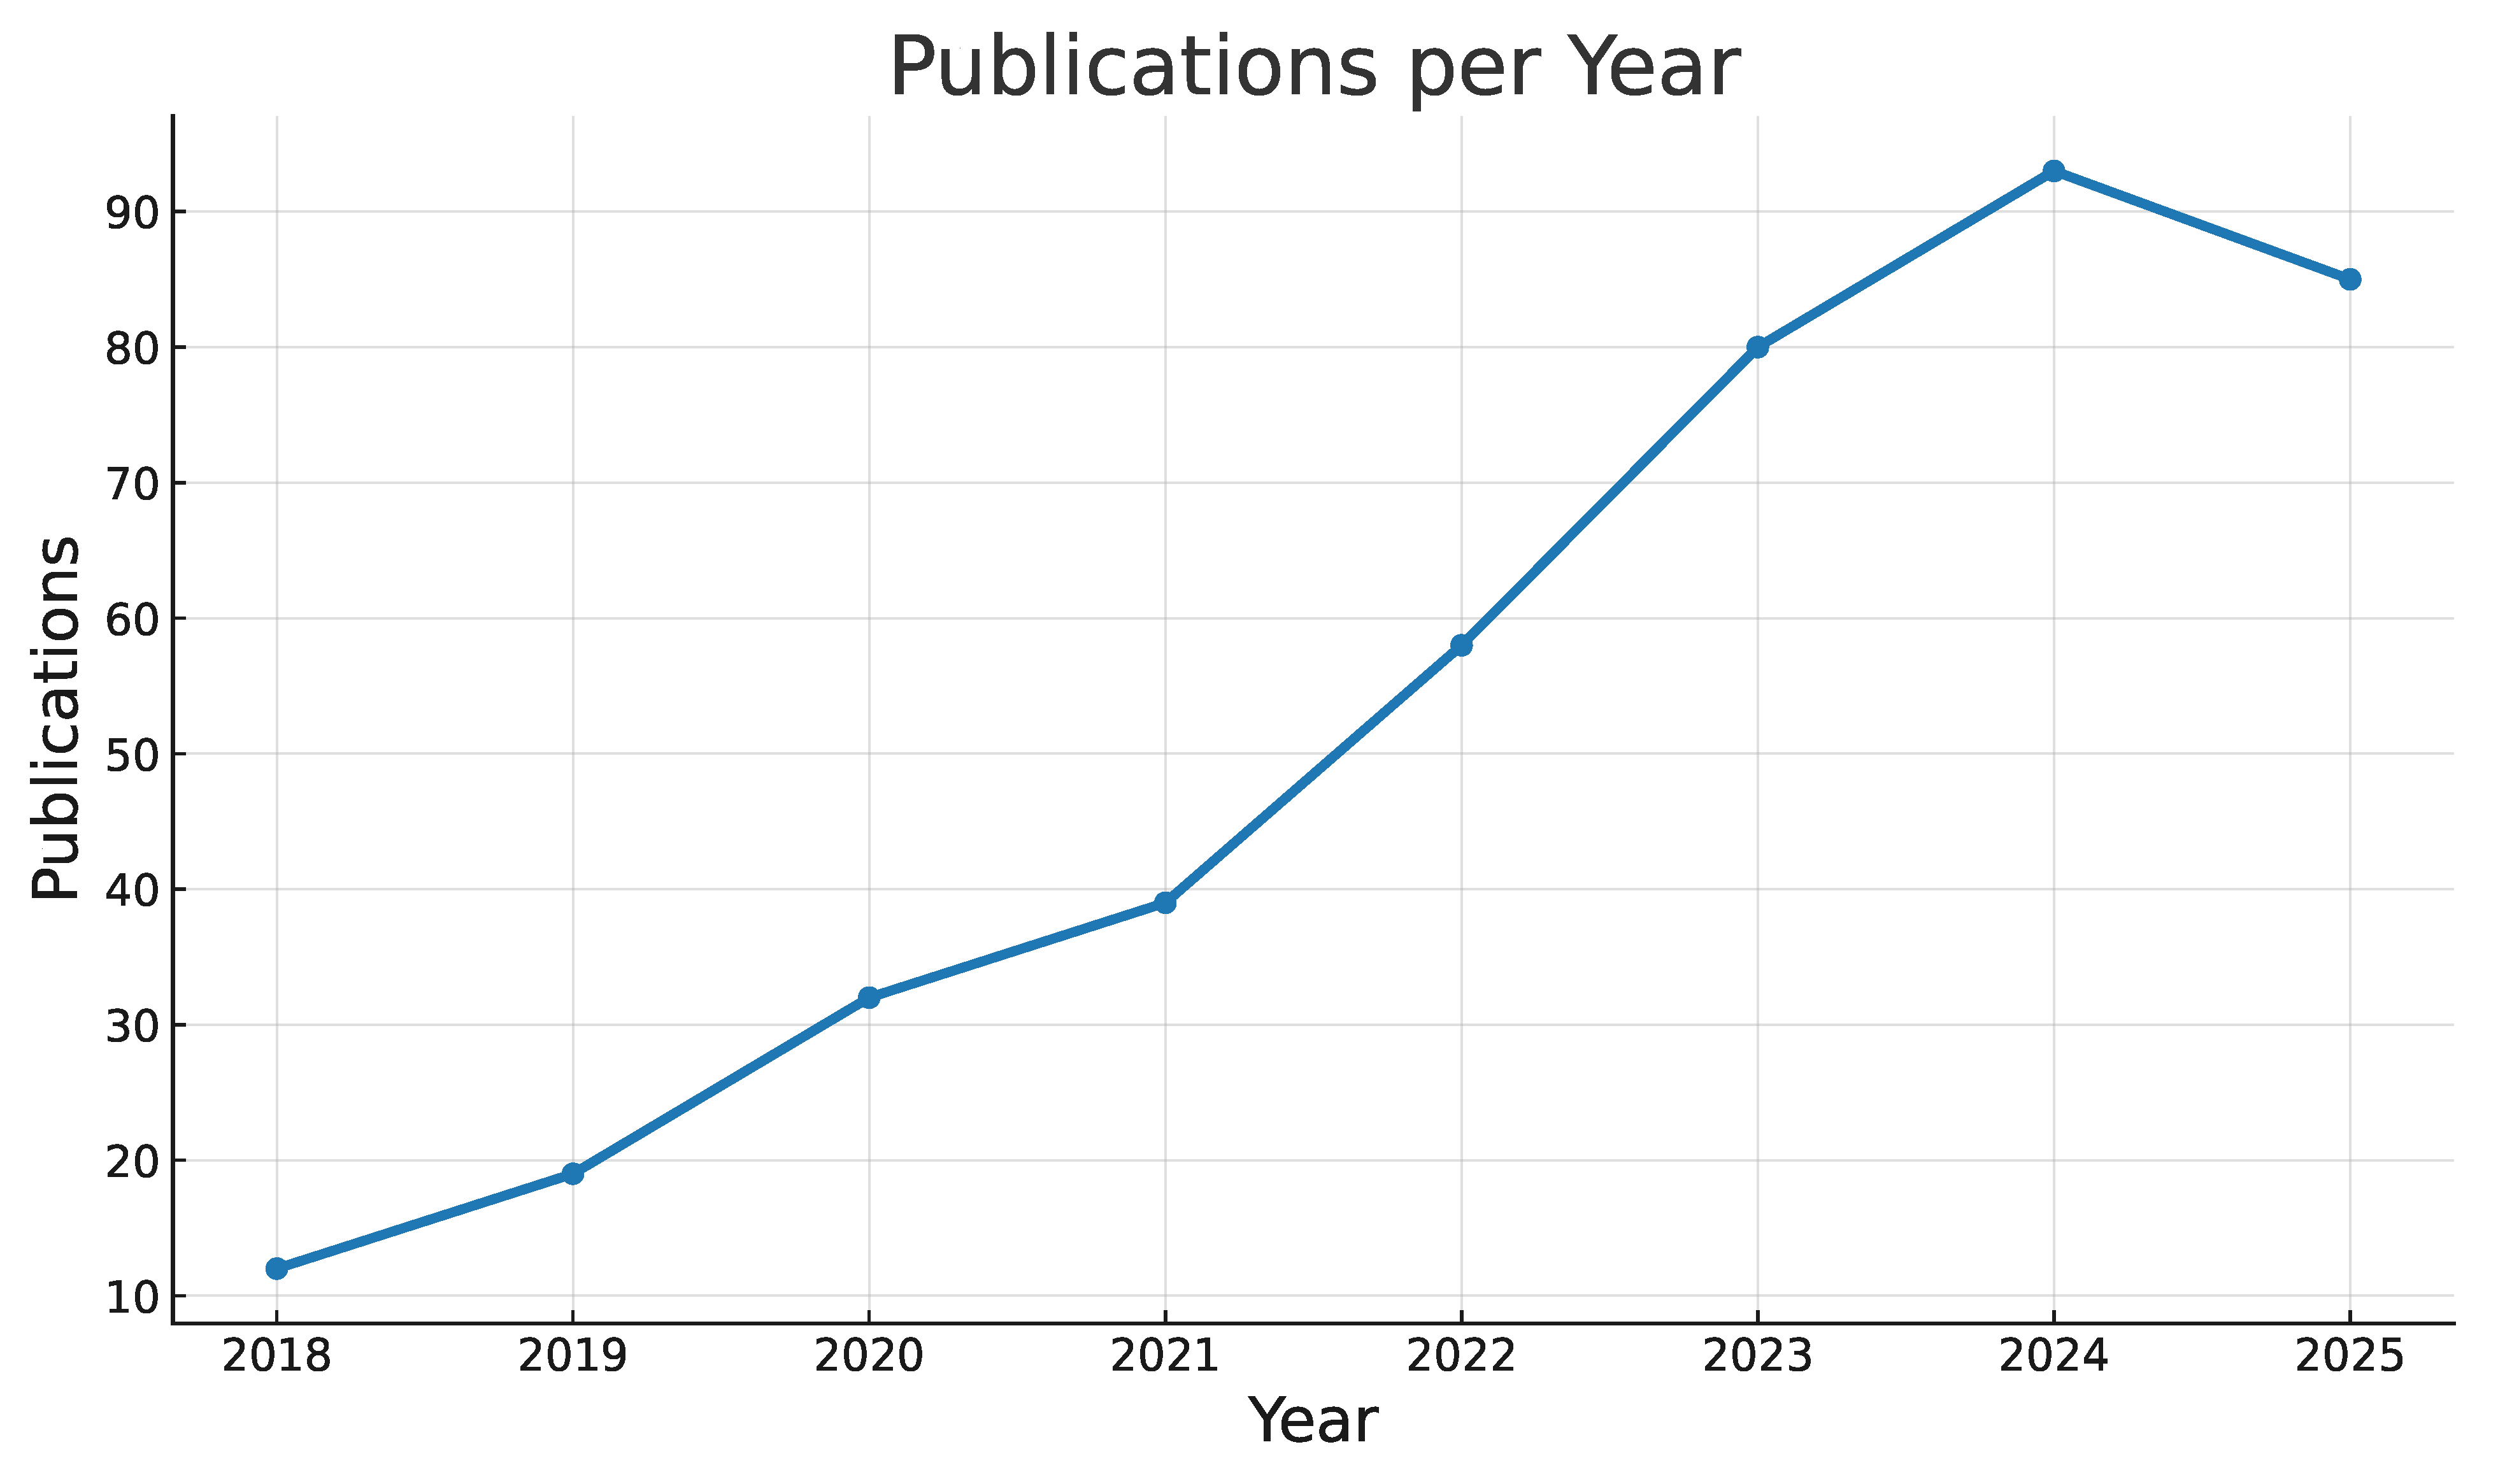
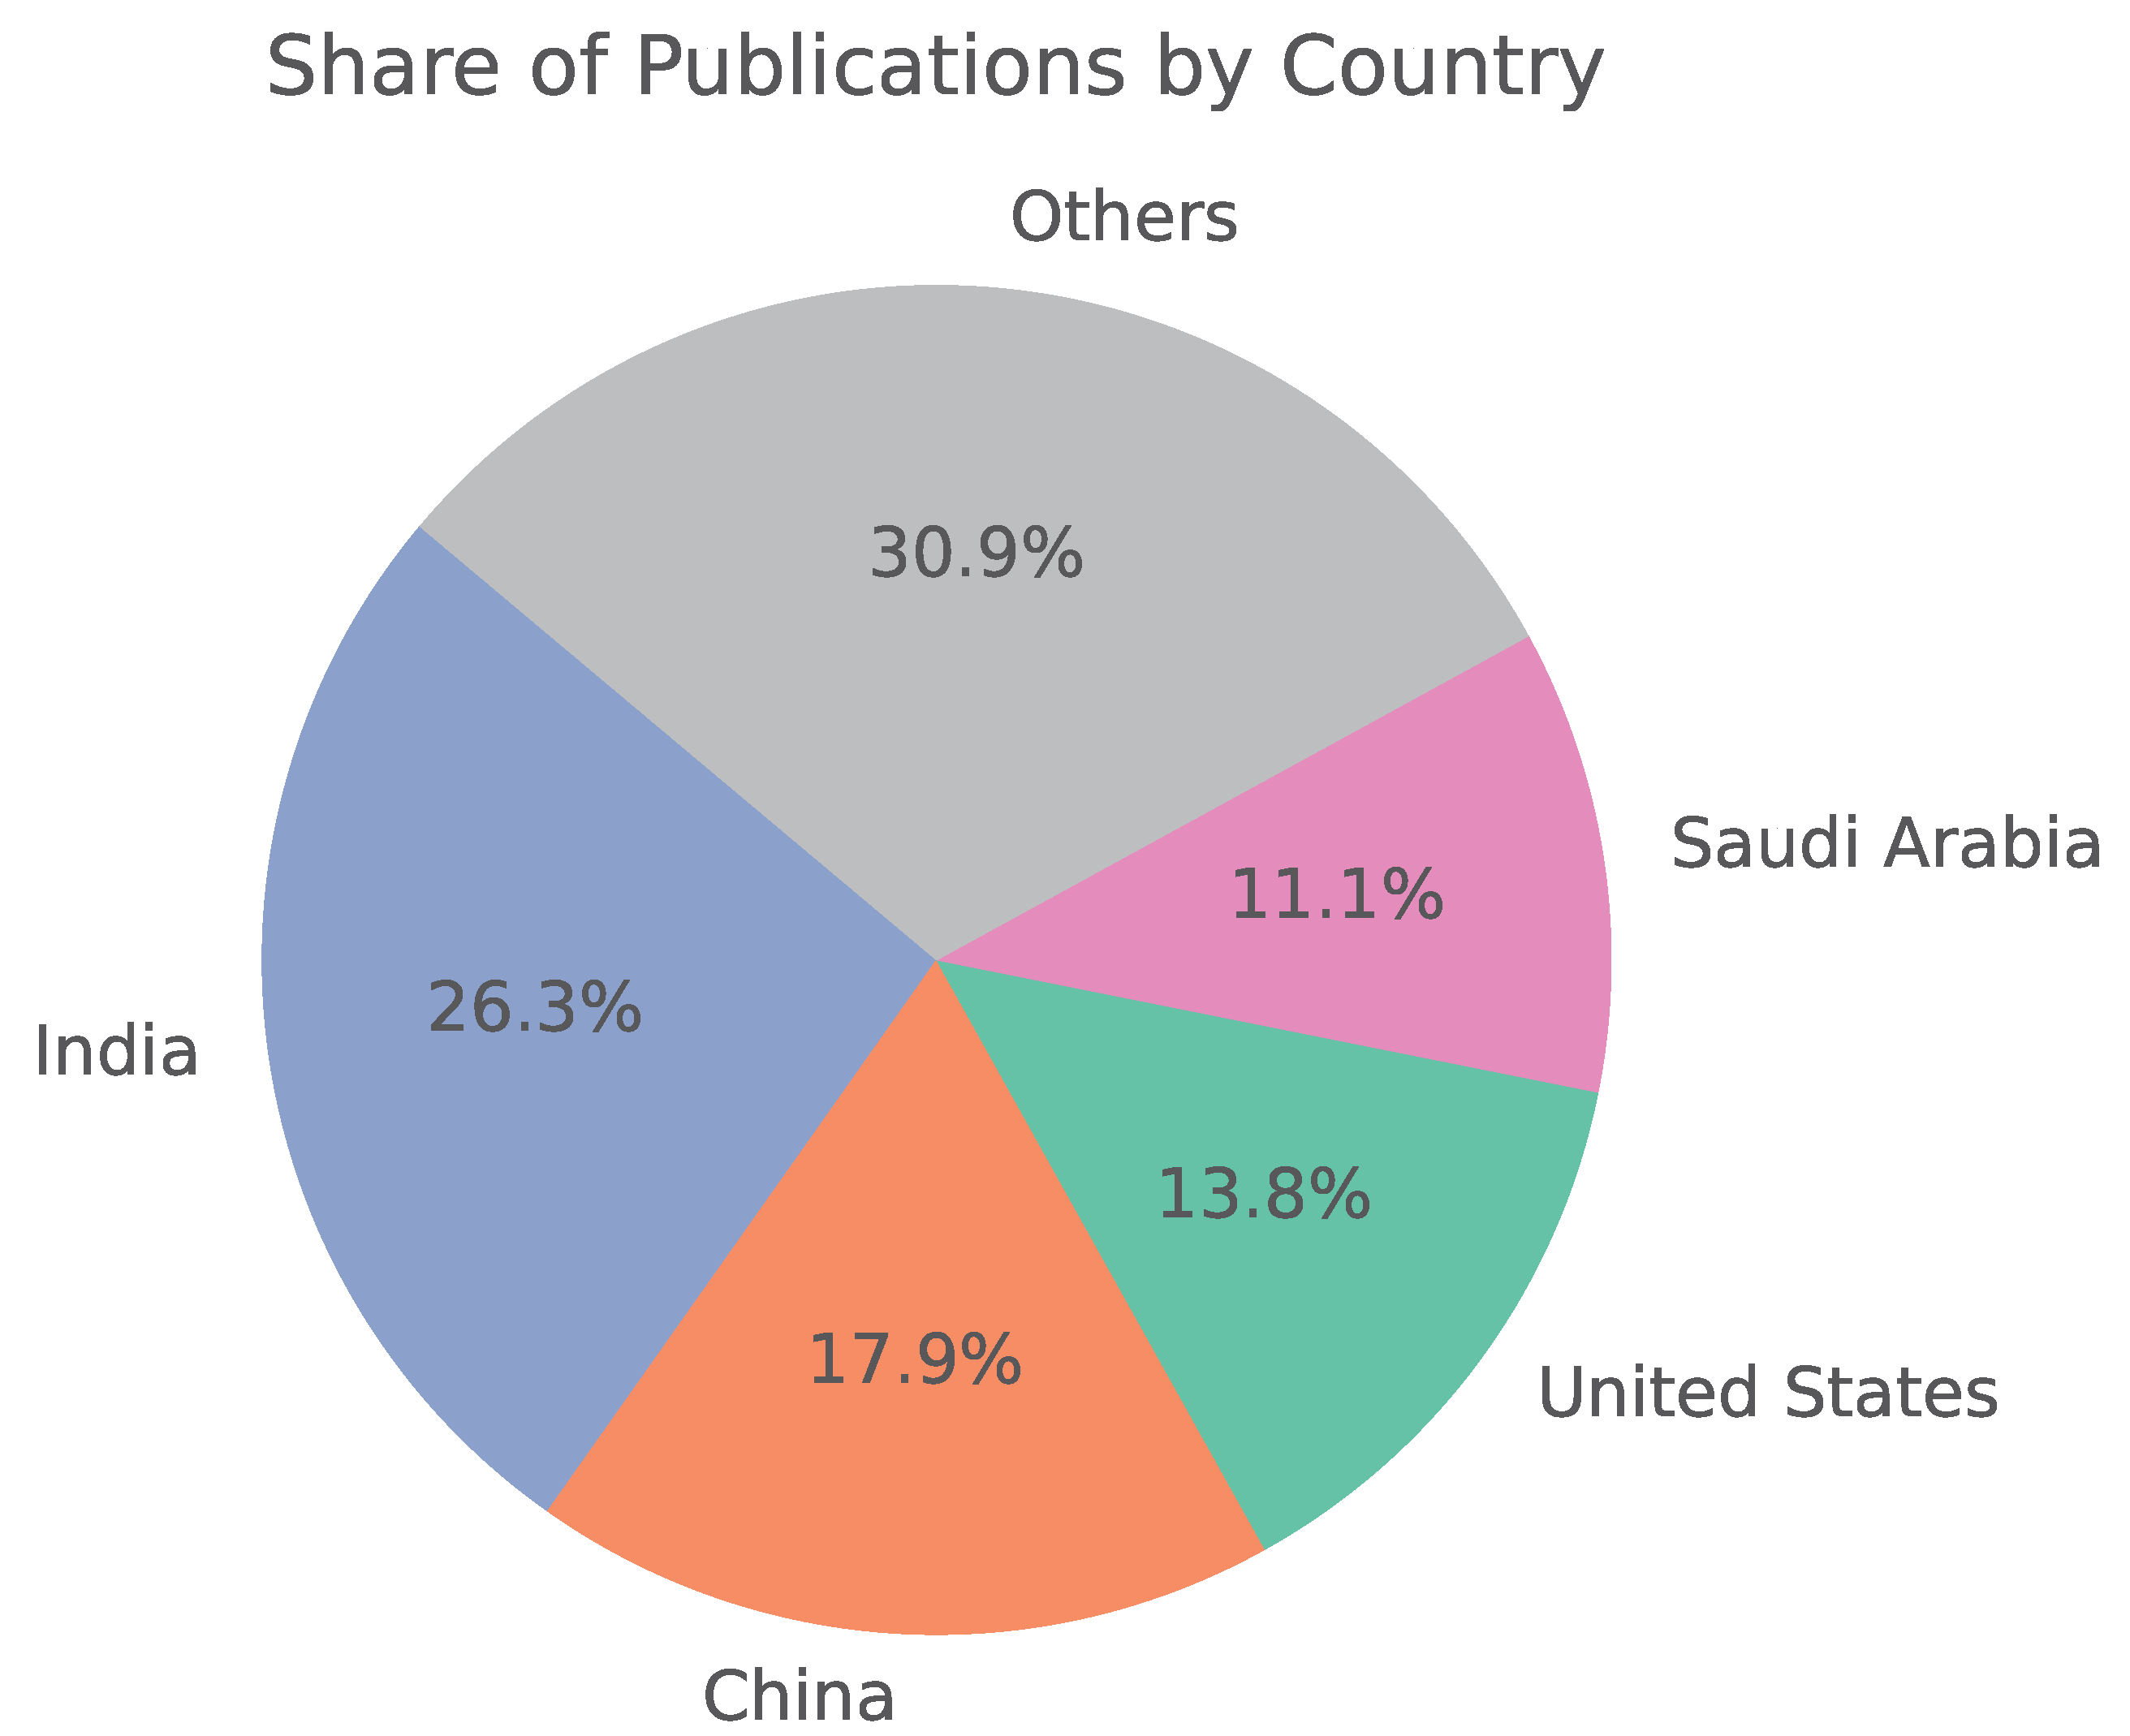
The data, shown in Figure 2, demonstrate a clear upward trend in the number of publications, peaking in 2024, indicating growing scientific interest in the application of AI in hematopathological diagnostics. It is also interesting to see the main contributors by country—this is shown in Figure 3.
Figure 2.
Number of publications per year over the analyzed period.
Figure 3.
Percentage share of publications by the top four contributing countries and others.
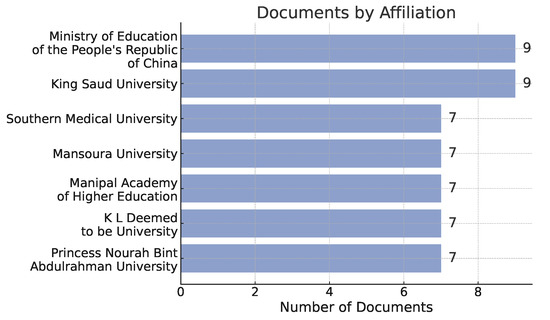
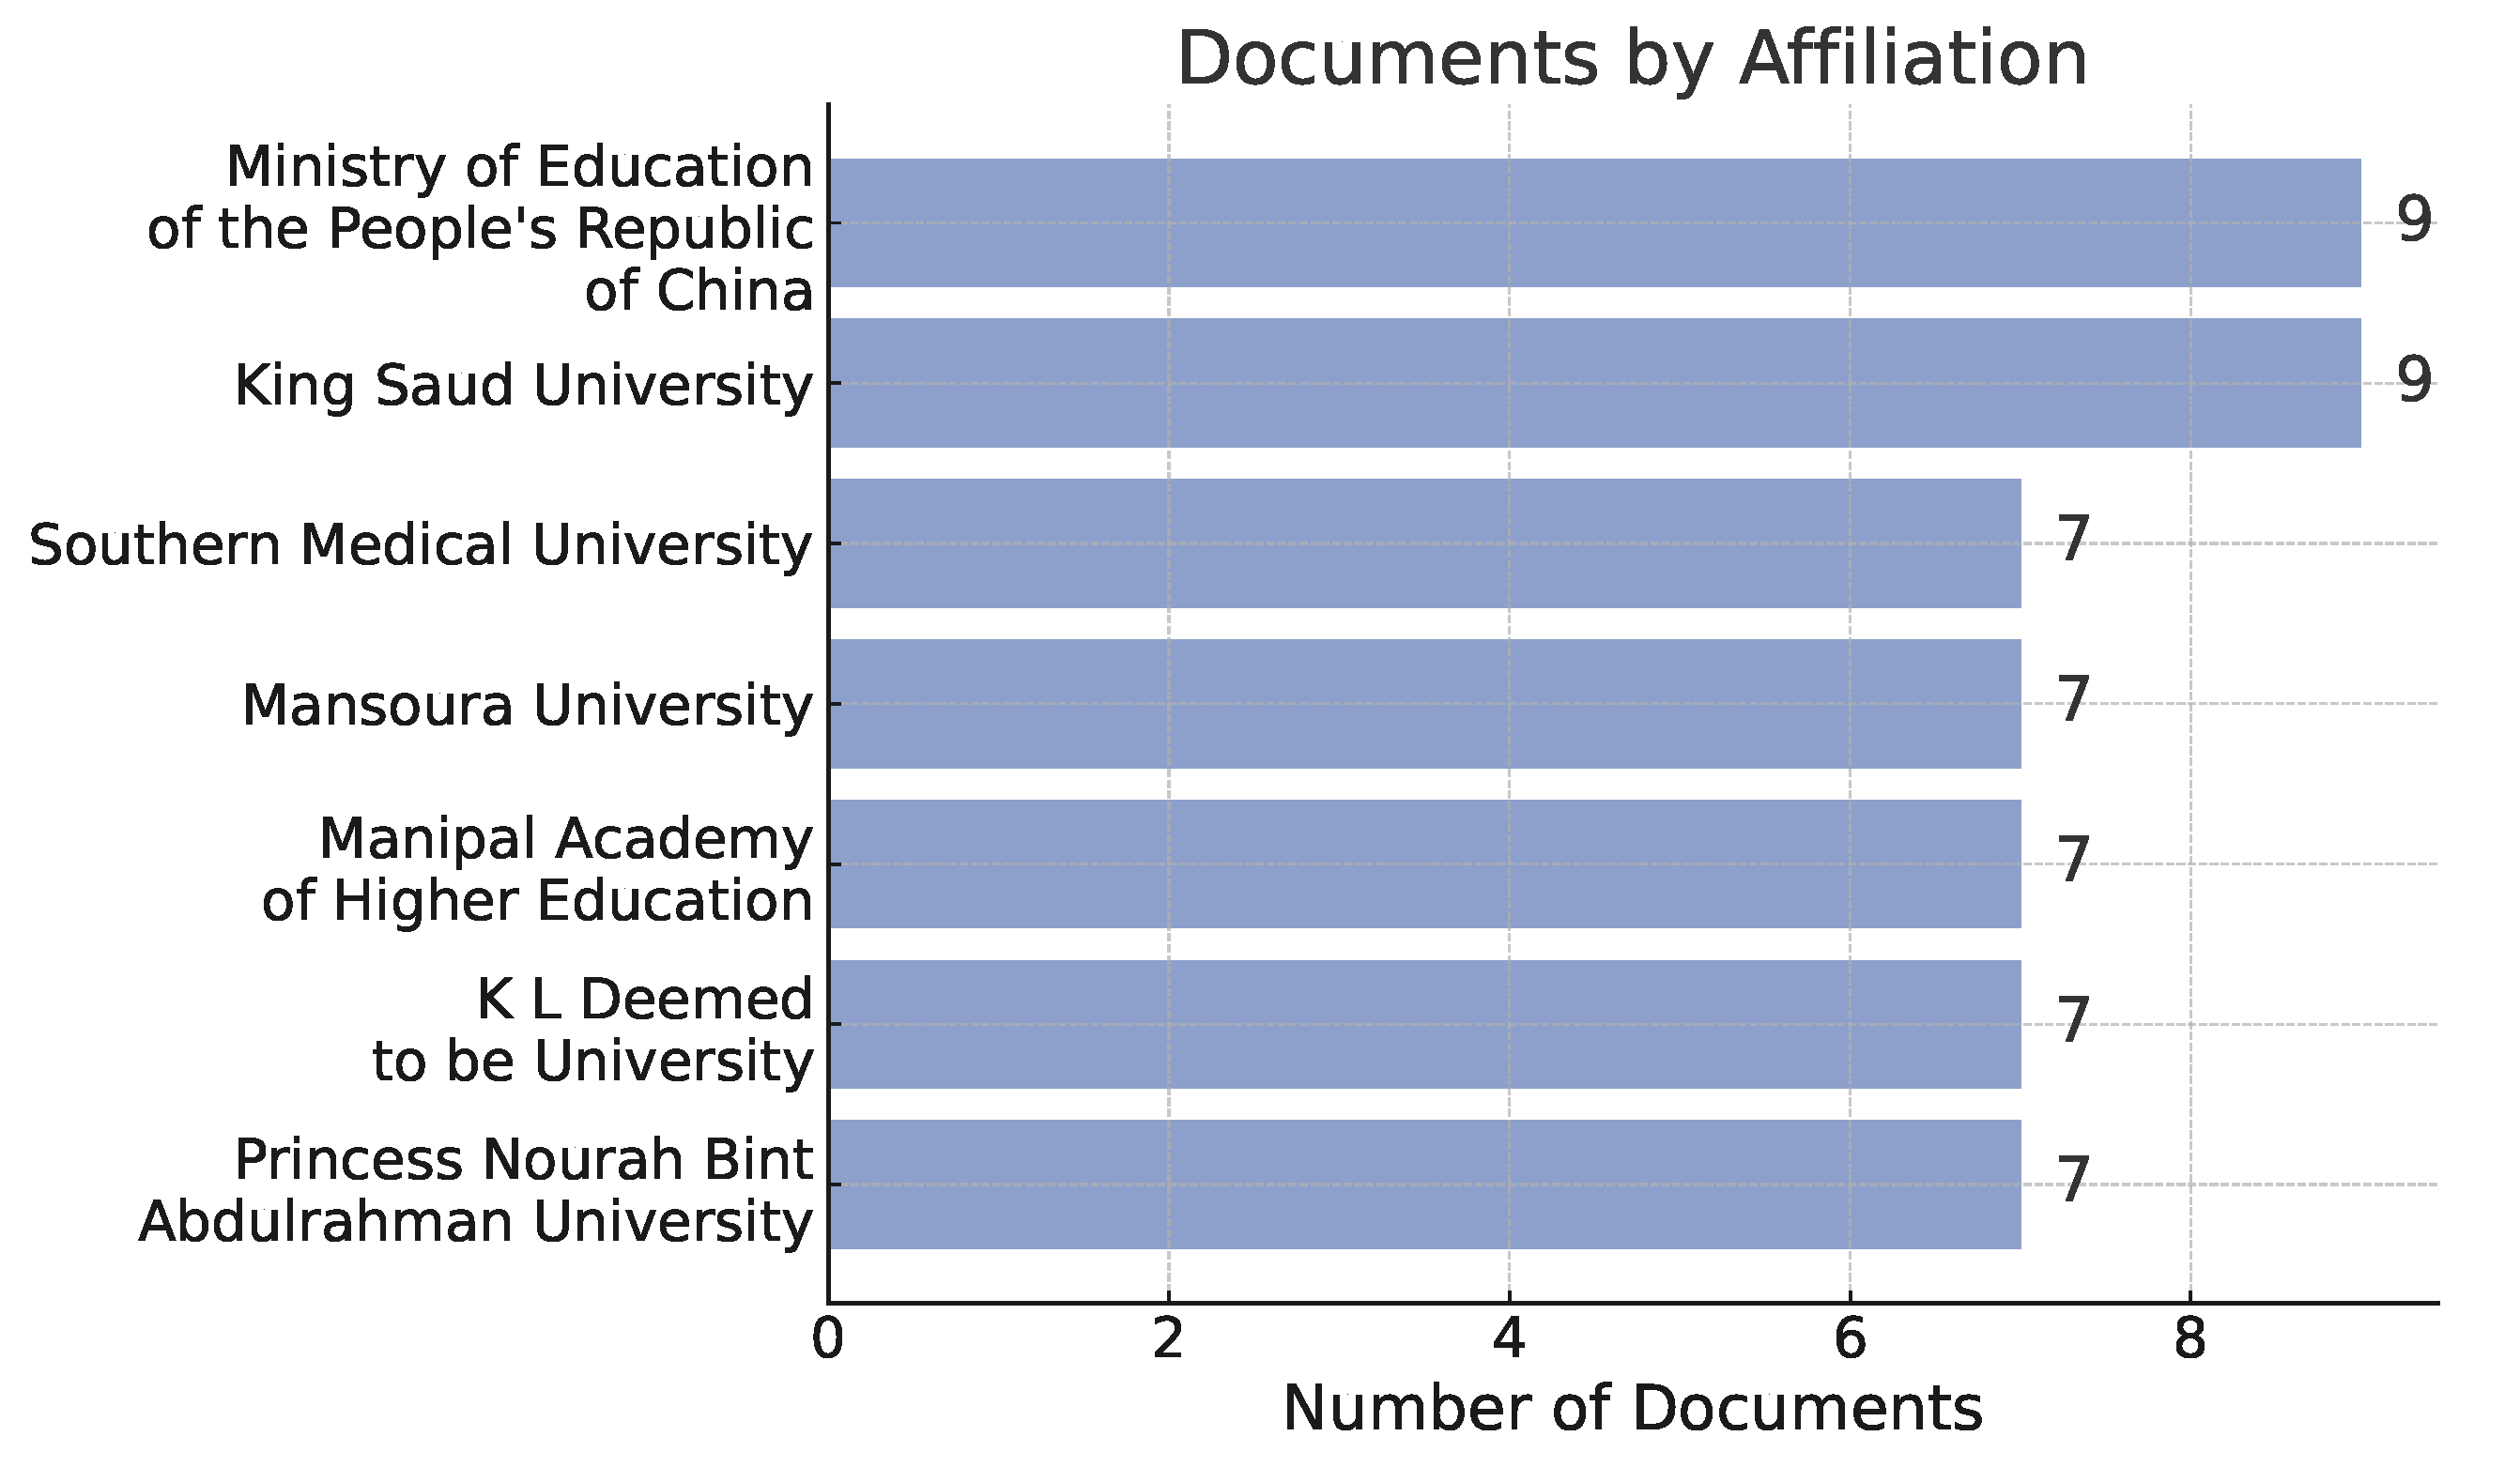
Institutional contributions are visualized in Figure 4, where the most active research centers are listed. Notably, several universities in Asia and the Middle East are among the top contributors, reflecting global academic interest beyond traditionally dominant regions.
Figure 4.
Number of publications by the most active research institutions.
3.3. Limitations
This bibliometric analysis is based exclusively on data retrieved from the Scopus database, which may limit its comprehensiveness in capturing the global scientific output—particularly in comparison to other databases such as Web of Science or PubMed. However, the choice of Scopus was deliberate. In addition to its broad interdisciplinary coverage spanning biomedicine, computer science, and engineering, Scopus indexes a substantial share of AI-relevant conference proceedings (e.g., IEEE/ACM) that are underrepresented in PubMed and inconsistently covered by Web of Science. For the bibliometric component, Scopus provides standardized author and affiliation identifiers, controlled keywords, funding information, and complete reference–citation linkages, which together enable reproducible de-duplication, network mapping, and longitudinal trend analyses. Relying on a single, internally consistent corpus also reduces cross-database heterogeneity in indexing practices and document-type definitions that could bias comparative indicators. Finally, Scopus offers robust export and API options (including citation fields and abstracts) that facilitated the complex filtering and data-processing steps applied in this review. Furthermore, the analysis was conducted based on titles and abstracts without a full-text screening, which may have led to the omission of some relevant publications (false negatives) or the inclusion of articles only marginally related to the topic (false positives). The employed search algorithms relied on keyword matching, which increases the sensitivity of the analysis but may reduce its precision in the case of non-obvious formulations or interdisciplinary studies. Additionally, the citation counts were analyzed based on the data available at the time of extraction, meaning that these values are dynamic and may change over time.
3.4. Conclusions
This prepared bibliometric analysis demonstrates a clear increase in the number of publications addressing the application of artificial intelligence in histopathological diagnostics of leukemias in recent years, with a particularly notable acceleration observed between 2021 and 2024. This indicates a growing scientific interest in this research area and highlights the increasing importance of AI methodologies in hematological diagnostics. Furthermore, the analysis of article types reveals the predominance of studies focusing on deep learning methods, particularly convolutional neural networks, as well as the development of clinical decision support systems. The highest research activity is observed among institutions from China, India, the United States, and Saudi Arabia, reflecting the global and multi-center nature of work in this field. The affiliation analysis also shows that research is conducted both at large universities and smaller research centers, indicating widespread interest across various levels of the scientific community.
4. Datasets
This section offers an overview of available databases for the development and evaluation of medical image analysis models. In the context of leukemia diagnostics, these datasets offer annotated images that enable both training and benchmarking of AI-based diagnostic models. Table 2 summarizes 43 such datasets related to leukemia, detailing their publication year, number of images, resolution, magnification, diagnostic focus or task type, number of citations, and material source.
Table 2.
An overview of datasets used to train leukemia-recognition models.
5. Image Processing Methods Used for Histopathological Diagnostics of Leukemias
Medical images contain a large amount of unstructured information, and their use in leukaemia diagnosis requires significant expertise. Image processing allows part of the diagnostic workflow to be automated. In this process, analysis methods are applied to medical images to organise the data and extract the most relevant features. One of the key steps in this process is segmentation, which involves the division of pixels into mutually exclusive groups. A fundamental method of segmentation is thresholding, where pixels are assigned to classes based on a threshold T. A key aspect of thresholding is the appropriate selection of threshold T. In many methods, this value is determined through histogram analysis. A comparative study of automatic threshold selection algorithms based on histogram analysis is presented in [71]. Thresholding is a fast operation, but when applied alone it is ineffective. Therefore, it is typically used as a preliminary step within a classification. This approach has also been used in the AI models for leukemia diagnosis, as reported in [36,43,46,64,66,68,72]. The models achieved accuracies ranging from 85% to 99.12%.
In medical image analysis, segmentation is typically followed by classification. One of the simplest classifiers is k-nearest neighbor (KNN). In this approach, a reference dataset, divided into classes (e.g., types of diagnoses), is used. During classification, the distance (e.g., Eucidean distance) to the known reference cases is calculated. The class most commonly occurring among the k nearest neighbors is assigned to the new instance. Among the AI models presented in Table 3, those presented in [33,34,36,46,52,64,72,73,74,75] incorporate KNN as part of their methodology. The overall models have been been successfully applied in leukaemia detection, which reported accuracy ranging from 85.8% to 99.61%. Another simple classifier is the Decision Tree (DT). It operates as if–else conditions, which can be visualized as a tree composed of decision nodes. In the classical approach, each condition is based on a single feature, and each terminal node (leaf) corresponds to a specific feature used to assign a label to a new instance [76]. Among the AI models listed in Table 3, those presented in [33,34,72] include DT, with reported accuracy in ranging from 85% to 99.14%. An extension of the decision tree concept is Random Forest (RF) [77], which combines the outputs of multiple independently constructed trees. Each tree is trained on a randomly selected bootstrap sample of the training data, and feature bagging is applied at each decision point by selecting a random subset of features. This double randomization reduces variance and helps prevent overfitting. Classification is performed by aggregating the predictions of all trees, typically through majority voting or probability averaging [77]. Among the AI models listed in Table 3, those presented in [33,34,36,52,72,73,74] incorporate RF, with reported accuracy ranging from 85% to 99.61%.
Besides supervised classifiers, unsupervised methods are also applied in medical image analysis, where data are grouped without predefined labels. One of the most widely used approaches is the k-means clustering algorithm. It partitions data into k disjoint groups, called clusters. The number of clusters k is defined prior to training. The clustering is performed by minimizing the within-cluster sum of squares (WCSS), i.e., the sum of squared Euclidean distances between data points x and their assigned cluster centroids . The loss function is formally defined in Equation (1). It aggregates the squared distance between each of the n data points x and the centroids of the cluster to which it is assigned. The set denotes all data points x assigned to cluster j. The corresponding cluster centroid is denoted by .
The k-means minimize the loss function by iteratively refining the assignment of data points x and the positions cluster centroids . At each iteration, the algorithm performs two alternating steps:
- Assignment step—each data point is assigned to the cluster whose centroid is closest.
- Update step—for each cluster , the centroid is updated as the mean of the data points assigned to cluster , as shown in Equation (2).
These two steps are repeating until convergence, typically when cluster assignments stabilize or the decrease in falls below a set threshold [78]. Among the AI models presented in Table 3, those presented in [58,68,75,79,80] incorporate k-means clustering algorithm. Their reported accuracy ranges from 94.23% to 100%.
While clustering methods group data without labels, many supervised classification techniques rely on a linear combination of features x with weights w. This combination is expressed by the function presented in Equation (3). This concept forms the basis of linear regression. It can be applied to regression problems, predicting a real-valued number. Without additional modifications, the method is not suitable for classification tasks [76].
The linear function (3) also forms the basis of the binary classifier Support Vector Machine (SVM). Applying the function to the linear function (3) yields the SVM decision function, as shown in Equation (4).
The output is either or , representing two distinct classes, and the training objective is to maximize the separation between these classes. It is done by maximizing the margin, defined as the distance between the decision boundary and the nearest data points. It has been observed that the classification boundary is determined by a small subset of the training data, known as support vectors [81], which lie closest to the margin. Among the AI models presented in Table 3, those presented in [33,34,36,45,46,52,58,59,60,61,62,63,64,68,72,73,74,75] incorporate SVM. Their reported accuracy ranges from 82% to 99.61%.
Leukemia detection from images is commonly performed using artificial neural networks (ANNs), such as the multilayer perceptron (MLP), a feedforward ANN composed of layers of units called neurons. The network consists of an input layer, one or more hidden layers, and an output layer producing the prediction . Each neuron computes a linear combination of its inputs, as in Equation (3), and applies a nonlinear activation function to produce the output. A schematic of single-neuron MLP with activation is shown in Figure A1. It illustrates the linear combination of inputs and weights represented as a circle, followed by the sigmoid activation function shown as a rectangle, producing the output prediction .
MLP generalizes this concept by stacking multiple neurons into layers with various activation functions. In a standard MLP, each neuron in a given layer receives as input all outputs from the neurons in the preceding layer. This type of connection is referred to as a fully connected (FC) or dense layer [76]. A schematic of such a network is presented in Figure A2. It consists of a single input layer with five inputs, denoted as . There are two hidden layers, each containing three neurons. The first hidden layer includes neurons , and the second hidden layer includes neurons . Finally, there is a single output . Among the AI models presented in Table 3, those reported in [45,60] use MLP for leukemia diagnosis. Their reported accuracy ranges from 96.67% to 97%.
Convolutional Neural Network (CNN) extends the concept of MLP by incorporating convolutional layers that automatically extract local features.One of the first successful CNNs, LeNet-5 [82], is presented schematically in Figure A3. Convolutional layers in LeNet-5 [82] were designed to enable the local extraction of features such as edges, corners, and textures without the need for manual feature engineering. The mathematical formulation of a convolutional layer is presented in Equation (5), where X denotes the input to the layer, K is the convolutional kernel, b is the bias term, is the activation function, and Y represents the output of the layer.
Convolution is performed by sliding the filter K across the spatial dimensions of X.
In classical CNN architectures, convolutional layers are typically followed by pooling layers. A pooling layer operates similarly to a convolutional layer, sliding a fixed size window (e.g., ) over the input matrix. However, instead of computing a weighted sum, it applies an aggregation function. Common choices include the maximum (max pooling) or the average (average pooling). Pooling layers do not contain trainable parameters. Their behavior remains fixed during both training and evaluation.
The convolutional and pooling layers produce a multi-dimensional feature map, typically represented as a 3D matrix. To enable classification, this feature map is flattened into a one-dimensional vector by a flatten layer. The flattened representation is then passed to a fully connected network, structurally identical to a traditional multilayer perceptron (MLP). These layers generate the final prediction, such as a classification.
Among the AI models for leukemia diagnosis summarized in Table 3, those presented in [30,38,43,52,66,72,79,80] use CNN. Their reported accuracy ranges from 85% to 100%.
An extension of the classical CNN approach is a Deep Convolutional Neural Network (DCNN) AlexNet. This architecture is proposed in [83], which achieved first place in the ImageNet ILSVRC-2012 competition. A schematic overview of the AlexNet is presented in Figure A4. This neural network consists of 15 layers, including five convolution layers and three dense layers. Among the AI models for leukemia diagnosis summarized in Table 3, those presented in [36,37] incorporate AlexNet architecture. Their reported accuracy ranges from 97.5% to 99.12%.
Deep convolutional neural networks were further developed by Simonyan and Zisserman from the Visual Geometry Group (VGG) at the University of Oxford [84]. In their work, six model variations were introduced, differing in number of parameters and depths of 11, 13, 16 and 19 layers. The architecture employs convolutional layers with filters and same padding, ensuring that the spatial dimensions of the input and output feature maps remain identical. These convolutional layers are grouped into blocks. Each block contains two to four consecutive layers followed by a max pooling layer. An example of such a module, containing three convolutional layers and a single max pooling layer, is shown in Figure A5. The VGG network [84] is composed of five such blocks, each with a varying number of convolutional layers, followed by three fully connected (FC) layers at the end. The most commonly used version of the VGG neural network is VGG16, where 16 refers to the version with a total of 16 learnable layers: 13 convolutional and 3 fully connected layers. The convolutional layers are distributed across the five blocks as follows: 2, 2, 3, 3 and 3. Among the AI models for leukemia diagnosis summarized in Table 3, those presented in [34,36,46,53,54,70] incorporate VGG16 architecture. Their reported accuracy ranges from 94.02% to 99.17%.
An extension of the deep convolutional network concept to very deep architectures is ResNet [85]. Its key innovation is the introduction of skip connections, which create a direct pathway between the input and output of a block. An example of such a block is shown in Figure A6 where the input x is passed through two convolutional layers, Conv1 and Conv2, producing an intermediate output . The input x is then added to this output, resulting in , followed by a ReLU activation.
Skip connections allow the network to skip certain layers through residual learning, thereby improving gradient propagation. It effectively addresses the vanishing gradient problem and enables the training of very deep networks. In [85], authors evaluated architectures from 20 do 1202 layers. In practice, commonly used ResNet variants include ResNet-18, ResNet-34, ResNet-50, ResNet-101 and ResNet-152. Among the AI models for leukemia diagnosis summarized in Table 3, those presented in [34,36,42,51,53,54] incorporate ResNet architecture. Their reported accuracy ranges from 93.8% to 99.17%.
An extension of the ResNet, referred to as ResNeXt, was proposed in [86]. Its key component is a transformation block that incorporates multiple parallel convolutional paths. A schematic representation of a typical ResNeXt block is presented in Figure A7. Each path, also referred to as a cardinality branch, processes the input x independently using a sequence of convolutional layers. The number of paths is defined by a hyperparameter known as cardinality [86]. The usual configuration of each path includes three convolutional layers per path: , and . While the structure of these paths is identical, each utilizes separate, independently learned weights. The outputs of all paths are summed element-wide. This is then combined with the original input x via a skip connection, following the residual learning approach introduced in ResNet. ResNeXt was used in leukemia detection in [49], achieving an accuracy of 90%.
An extension of the skip connection concept from ResNet is realised in DenseNet [87] through the use of dense connection. In DenseNet, each layer receives as input a concatenation of the outputs from all preceding layers, rather than just from the immediate previous one. Each layer produces a fixed number of new feature channels, referred to as the growth rate, which are appended to the existing feature set. As a result, the number of channels increases linearly with network depth. To reduce feature dimensionality, dense blocks are inserted between transition layers, consisting of convolution followed by a pooling layer. The application of DenseNet to leukemia diagnosis was presented in [33,34], with reported accuracies ranging from 98.7% to 99.14%.
Extending the concept of deep convolutional networks, Inception [88] introduces parallel processing within an Inception module. In each module, the parallel paths perform different operations. The structure of a single Inception module is shown in Figure A8. This module contains four parallel branches, all of which receive the same input x:
- A sequence of followed by convolutions,
- A sequence of followed by convolutions,
- A max pooling followed by convolution,
- A single convolution.
The outputs of all paths are concatenated along the channel dimension. Inception combines the idea of multi-branch parallel processing from ResNetXt with the feature aggregation characteristic of DenseNet. However, unlike ResNet and DenseNet, Inception does not use skip connections. The application of Inception architecture to leukaemia diagnosis was presented in [53,54] with reported accuracy ranging from 94.02% to 99.17%.
An extension of the Inception is the use of depthwise separable convolutions, presented in Xception [89]. The structure of a single Xception block is shown in Figure A9. In the main processing path, a depthwise convolution is first applied. It is a spatial convolution performed independently on each input channel. This is followed by a pointwise convolution , which combines the output channels. Additionally, skip connections are employed between blocks, in a manner similar to ResNet. Xception extends the Inception architecture by using depthwise separable convolutions, which generalize the parallel convolutional paths used in Inception. It also incorporates skip connections, as introduced in ResNet. The application of Xception to leukaemia diagnosis was presented in [44] with reported accuracy of 96%.
Alongside the development of convolutional variants, an alternative approach based on the attention mechanism has been introduced. It was first applied in natural language processing and enables dependencies between all elements of a sequence to be analyzed simultaneously. The mechanism has since been adapted for computer vision, where an image is treated as a sequence of patches. This adaptation led to the development of Vision Transformers (ViT), which capture information in a global context. Their main disadvantage is the need for very large datasets for training. In addition, the inherent ability to detect local patterns, which is provided by convolutional networks, is absent. The application of the attention mechanism and vision transformers to leukemia diagnosis has been reported in [41,50,51], with accuracies ranging from 93.8% to 99.12%.
The presented methods are widely applied in the histopathological diagnosis of leukemias. A summary of selected scientific publications demonstrating the practical application of these methods is provided in Table 3.
Table 3.
Overview of existing AI models in leukemia diagnostics.
Table 3 summarises the review of publications on models for leukemia detection. The models employing classical methods include 20 classical models reported in [30,34,43,45,46,52,58,59,60,61,62,63,64,66,68,72,74,75,79,80] and 25 end-to-end models reported in [19,30,33,34,36,37,38,41,42,43,44,46,49,50,51,52,53,54,55,66,67,70,72,79,80]. A summary of comparison between these two paradigms is presented in Table 4. The average performance of models based on classical methods was found to be 96.34%, whereas that of end-to-end models was 97.72%, indicating that the difference between the two approaches is minimal.
Table 4.
Comparison of performance—classical vs. end-to-end methods.
Classical methods are characterized by the need for expert input in designing the processing pipeline and manually engineering preprocessing steps. As a result, learning is performed on preprocessed data, which allows models to be trained on relatively small datasets. These methods are considered explainable, since the function of each processing stage is clearly defined, and their interpretability provides strong potential for clinical adaptation. Nevertheless, a major limitation of classical approaches is their poor transferability to other problems or datasets, as the models rely heavily on manually designed features and task-specific preprocessing.
In the end-to-end approach, the model is treated as a black box, with learning carried out automatically. It does not require expert involvement but relies on larger datasets for training, and the resulting models are usually bigger and more computationally expensive than classical ones. The lack of explainability limits their clinical potential when compared with classical methods. However, they offer greater flexibility and easier adaptation to new problems, since no prior knowledge of features or expert input is required.
The models in [30,34,43,46,52,66,72,79,80] employ both classical and end-to-end methods. This makes it difficult to categorise them into a single paradigm, resulting in a hybrid approach. In this approach, the strengths and weaknesses of the two paradigms are combined. A balance is achieved in which a model may lean more towards the classical or the end-to-end design. The objective is to maximize the advantages of both while keeping the limitations at an acceptable level. Typically, expert knowledge is incorporated into preprocessing, where explainability supports clinical adaptation, dataset size requirements are reduced, and computational efficiency is improved. The subsequent stages are then processed in an end-to-end manner, ensuring flexibility and scalability. In this way, the hybrid approach provides a promising compromise between classical and end-to-end methodologies.
6. Discussion
The diagnostic process in pathology is a certain sequence of events that need to occur before we are able to reach a diagnosis. The tissue samples need to be collected, processed, fixated, transported onto slides and stained before we can watch them under our microscope [90]. These steps are necessary, but they also introduce errors (artifacts) in our slides, making their interpretation harder [91]. If we were to apply digital solutions, the process must also include scanning the slides so that they can be stored on a computer and analyzed by it. The scanning needs to keep the resolution good and the colors sufficiently preserved, and the technical parameters of the scanning device need to be of good quality. There is a wide selection of such scanning devices in the market [92], but their price might be a serious obstacle to the availability of AI-related diagnostic technologies in smaller/poorly funded laboratories. While scanning, we cannot remove or correct the slides as to get rid of artifacts—they are all preserved on the scanned image [93], making analysis by AI harder. The resolution and magnification of slides undergo changes when the slide is scanned and displayed on a monitor rather than under the microscope [94]. Difference in resolution might mean that some tiny, yet diagnostically important parts of the slide might no longer be seen on the slide version seen by the AI. Another diagnostic problem is that some tissue samples are only small pieces (biopsies) or are fragmented and their architecture is lost (e.g., many polyps obtained by endoscopy arrive fragmented)—fragmentation is another challenge that AI would have to overcome. While tissue fragmentation is not a problem in cytological specimens, this phenomenon if of utmost importance while diagnosing solid tumors or, e.g., lymphomas.
The AI models do not guarantee 100% perfection. An old Polish saying goes “only those who don’t do, don’t err”. In medicine, errors are an unavoidable part of medical practice in every specialization, including pathology. The sources of errors in diagnostics can be multifarious, including swapping the specimens or wrong storage/preparation [95]. Some of the errors are a consequence of simple clerical errors like mislabeling the slides [96]. Unfortunately, some wrong diagnoses are inevitably on the pathologists side. A study by Packer et al. [97] found that from 134 analyzed cases, 37 (27.6%) were diagnosed with a wrong entity. Nevertheless, trained pathologists can reach very high rates of success. A study by Dehan et al. [98] showed a remarkable rate of correct diagnoses in frozen intraoperative specimens (which due to their processing, have many artifacts and are more difficult for a pathologist to diagnose)—only 2.9 percent of errors in over 6000 samples. The use of artificial intelligence in diagnosing leukemias brought similar rates of success, with some models [64,66,67] reaching similar rates of accuracy in answering the given problem. However, it is important to note that all reviewed AI models were evaluated using retrospective histopathological datasets, which may not fully capture the variability encountered in routine clinical workflows. Such retrospective validation does not account for real-world factors like sample preparation differences, scanning artifacts variability, and integration challenges within existing diagnostic pathways. Prospective clinical validation studies are therefore urgently needed to assess real-world performance, generalizability, and impacts on diagnostic decision-making.
Even after a successful diagnosis in spite of the aforementioned error sources has been reached, not all problems are solved. According to the law, all pathology specimens need to be stored for a fixed amount of time to ensure the possibility of reviewing the diagnosis or solving eventual claims and disputes. In Poland, this obligatory storage period is 10 years in the case of cytological specimens and 20 years in the case of histopathology specimens [99]. The same requirement would obviously concern samples in virtual/digital form. If we realize that a single slide scanned occupies from 1 to 3 GBs [100], many cases consist of multiple slides from the same patient, and the demand for histopatological examinations is on the rise [101], one can easily imagine how high storage ability would be required from the laboratories to store all required by law data for such a long period. Such a large amount of data requires a lot of time to scan it—some slides may require 1000 s to be scanned [100].
Potential benefits of applying deep learning technologies in pathology are not limited to leukemias. A lot of models were already created for AI to help diagnose kidney pathologies [102], colorectal cancer [103], and prostate cancer [104]. Some of the models reached good results enough to be approved by relevant regulatory authorities (e.g., FDA in the case of the United States) and can be routinely employed to diagnose patients, the first of such algorithms accepted in 2021 [104]. Currently, the list of AI-based solutions approved by the FDA in various domains of medicine has 1247 entries; over 900 of them are from the radiology domain, with hematology having 19 entries and pathology 6 [105]. Since radiology is predominantly image analysis, technologies connected to it (similar to those presented in our review) are dominating the market of medical services. It seems that pathology, with only six registered entries up to date, still has many potential solutions to develop yet. Of these six entries, none of them is employed to analyze leukemia samples, and there are models trained for prostate slides analysis or gynecological cytology. Thus, none of the solutions presented in the article has obtained approval from the FDA to be employed in routine histopathological diagnostics.
A specific aspect of leukemias is that the diagnosis (as already mentioned in our article) cannot be reached based solely on microscopical slides. It requires a lot of additional examinations (genetic, cytometric) to reach the diagnosis. These techniques are outside the scope of our review.
A serious limitation of all AI-based models is that they cannot solve problems other than those for which they were created. Where a human pathologist can effortlessly switch between diagnosing cases from different systems of the human body in just a few minutes, such a change in the case of AI would require creating an entirely new model or a lot of training. Before fully replacing humans, AI would also need to learn how to integrate information from different diagnostic methods (flow cytometry, genetic methods), ordering and interpreting additional immunohistochemistry staining and keeping eyes open for artifacts and dust, which often distort the image to be seen on slides. Pathology cannot be reduced to black-white IT-like binary distinctions—it is the ability to see all shades of grey in between that enables us to reach accurate diagnoses. Time leaves open the question as to whether AI will ever be able to supplant human pathologists and, if yes, when this will happen.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/electronics14214144/s1, PRISMA 2020 Checklist and PRISMA 2020 Flow Diagram. Reference [106] is cited in the supplementary materials.
Author Contributions
Conceptualization, M.C.; methodology, G.R., A.Ż., P.K. and M.C.; software, P.K., P.M.T. and A.S.; validation, M.C. and P.K.; formal analysis, M.C., P.K., P.M.T., G.R., A.Ż. and A.S.; investigation, M.C., P.K., P.M.T., G.R., A.Ż. and A.S.; resources, M.C., P.K., P.M.T., G.R., A.Ż. and A.S.; data curation, M.C., P.K., P.M.T., G.R., A.Ż. and A.S.; writing—original draft preparation, M.C., P.K., A.S., P.M.T., G.R. and A.Ż.; writing—review and editing, M.C., P.K., A.S., P.M.T., G.R. and A.Ż.; visualization, P.K. and A.S.; supervision, G.R. and A.Ż.; project administration, M.C., G.R. and P.K. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
The data presented in this study are available in the Scopus® bibliographic repository (https://www.scopus.com, accessed on 12 July 2025) under institutional subscription. These data were derived from the peer-reviewed articles identified and included in this scoping review; full bibliographic details of all sources are provided in the reference section of the manuscript. No new primary datasets were generated or analyzed during the current study.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| WHO | World Health Organisation |
| AI | Artificial Intelligence |
| HTLV-1 | Human T-cell Lymphotropic Virus type 1 |
| ALL | Acute Lymphoblastic Leukemia |
| AML | Acute Myeloid Leukemia |
| CLL | Chronic Lymphocytic Leukemia |
| CML | Chronic Myeloid Leukemia |
| HCL | Hairy-Cell Leukemia |
| PLL | Prolymphocytic Leukemia |
| LGLL | Large Granular Lymphocytic Leukemia |
| MPAL | Mixed-phenotype Acute Leukemia |
| MM | Multiple Myeloma |
| FAB | French-American-British Classification |
| DIC | Disseminated Intravascular Coagulation |
| KNN | k-Nearest Neighbour |
| DT | Decision Tree |
| RF | Random Forest |
| GB | Gradient Boosting |
| LR | Logistic Regression |
| SVM | Support Vector Machine |
| RC | Ridge Classifier |
| MLP | Multilayer Perception |
| ANN | Artificial Neural Network |
| FC | Fully Connected |
| CNN | Convolutional Neural Network |
| DCNN | Deep Convolutional Neural Network |
| WCSS | Within-Cluster Sum of Squares |
| FPR | False Positive Rate |
| FNR | False Negative Rate |
| FDA | Food and Drugs Administration |
| VGG | Visual Geometry Group |
Appendix A
Figure A1.
A schematic diagram of the single neuron in MLP.
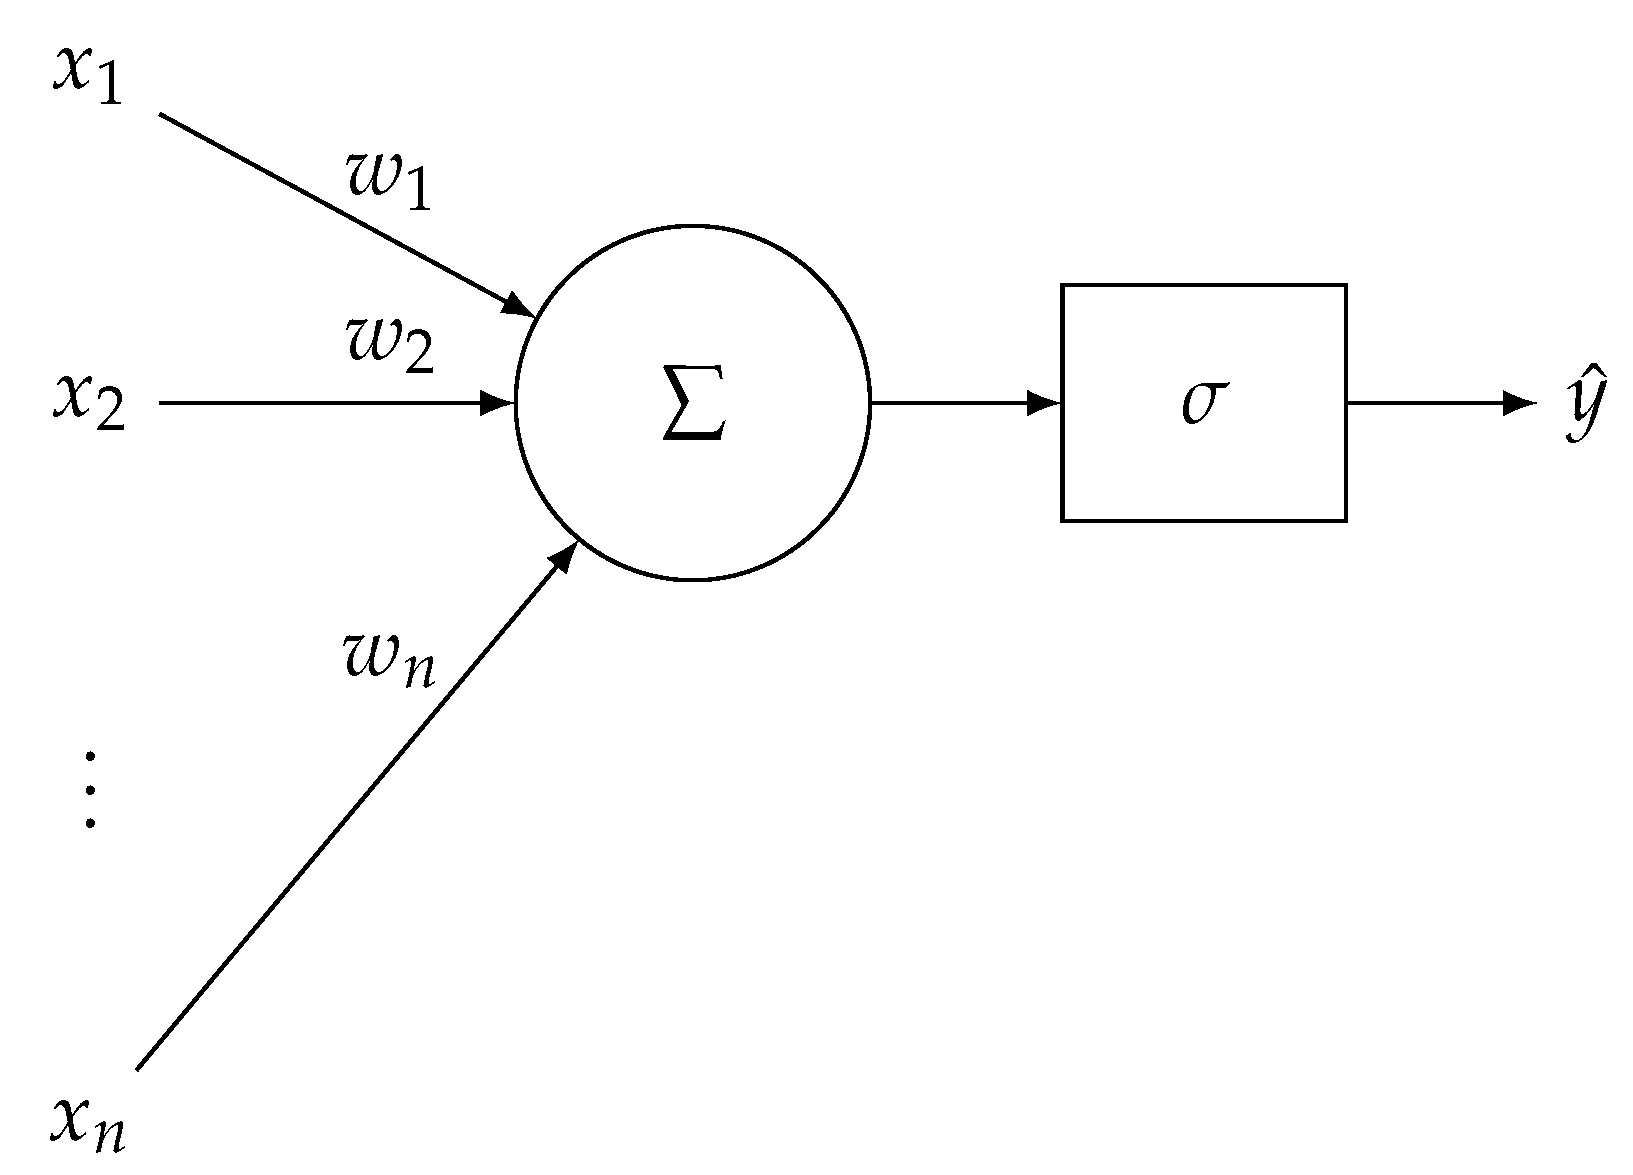
Figure A2.
A schematic diagram of MLP.
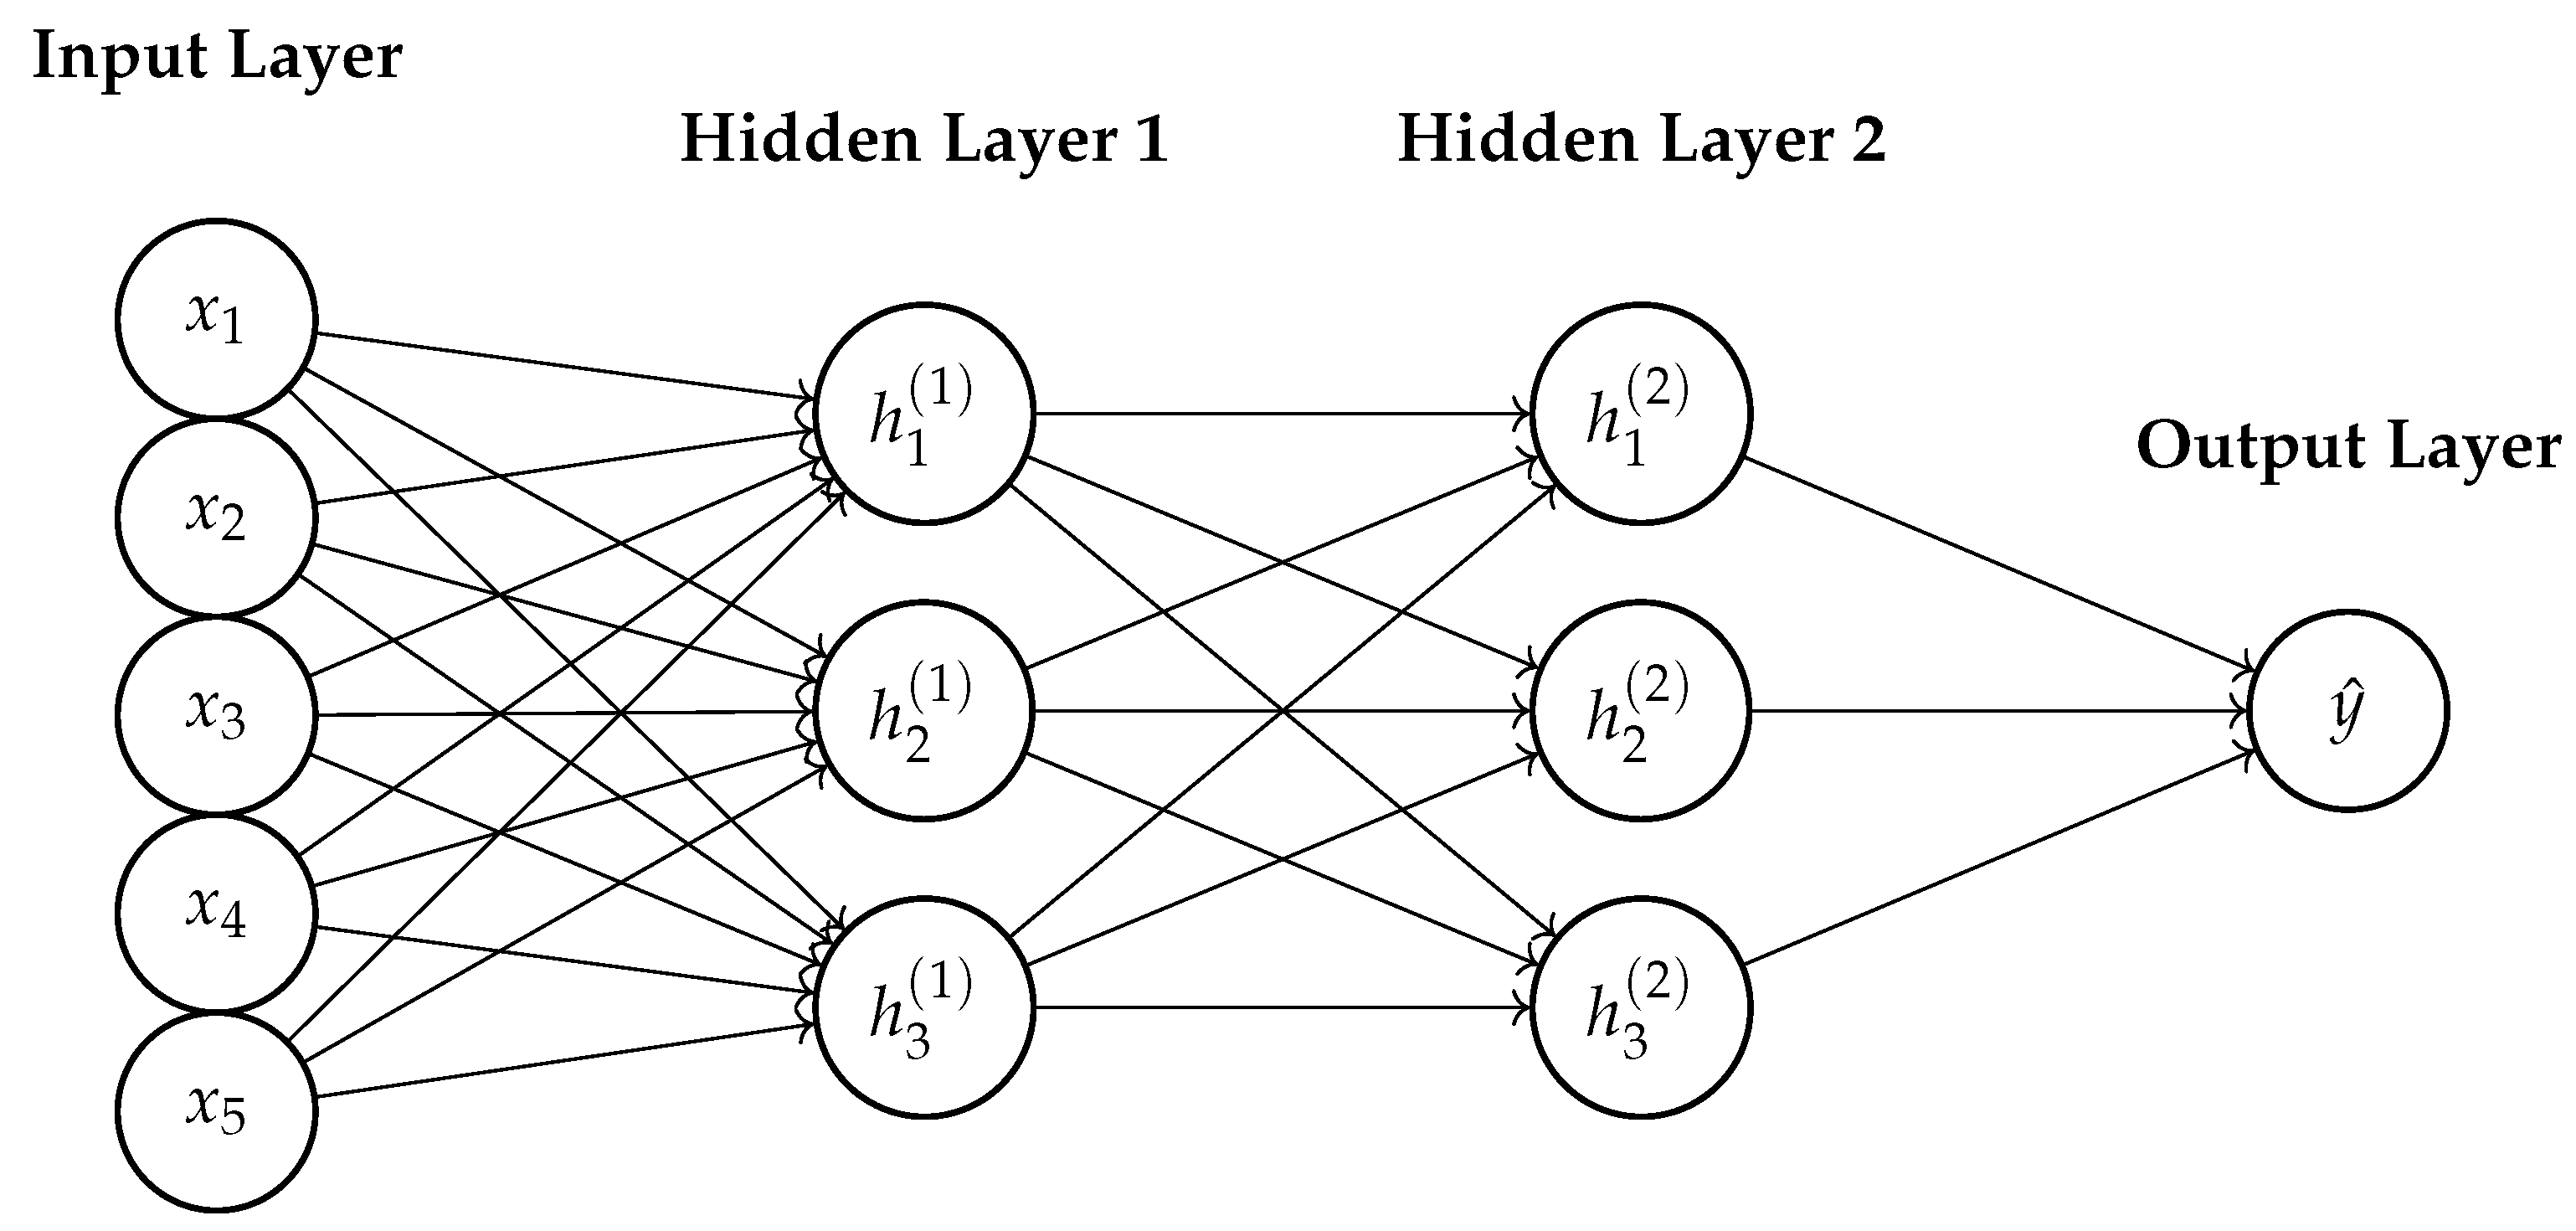
Figure A3.
A schematic diagram of the LeNet-5 architecture.

Figure A4.
A schematic diagram of the AlexNet architecture.
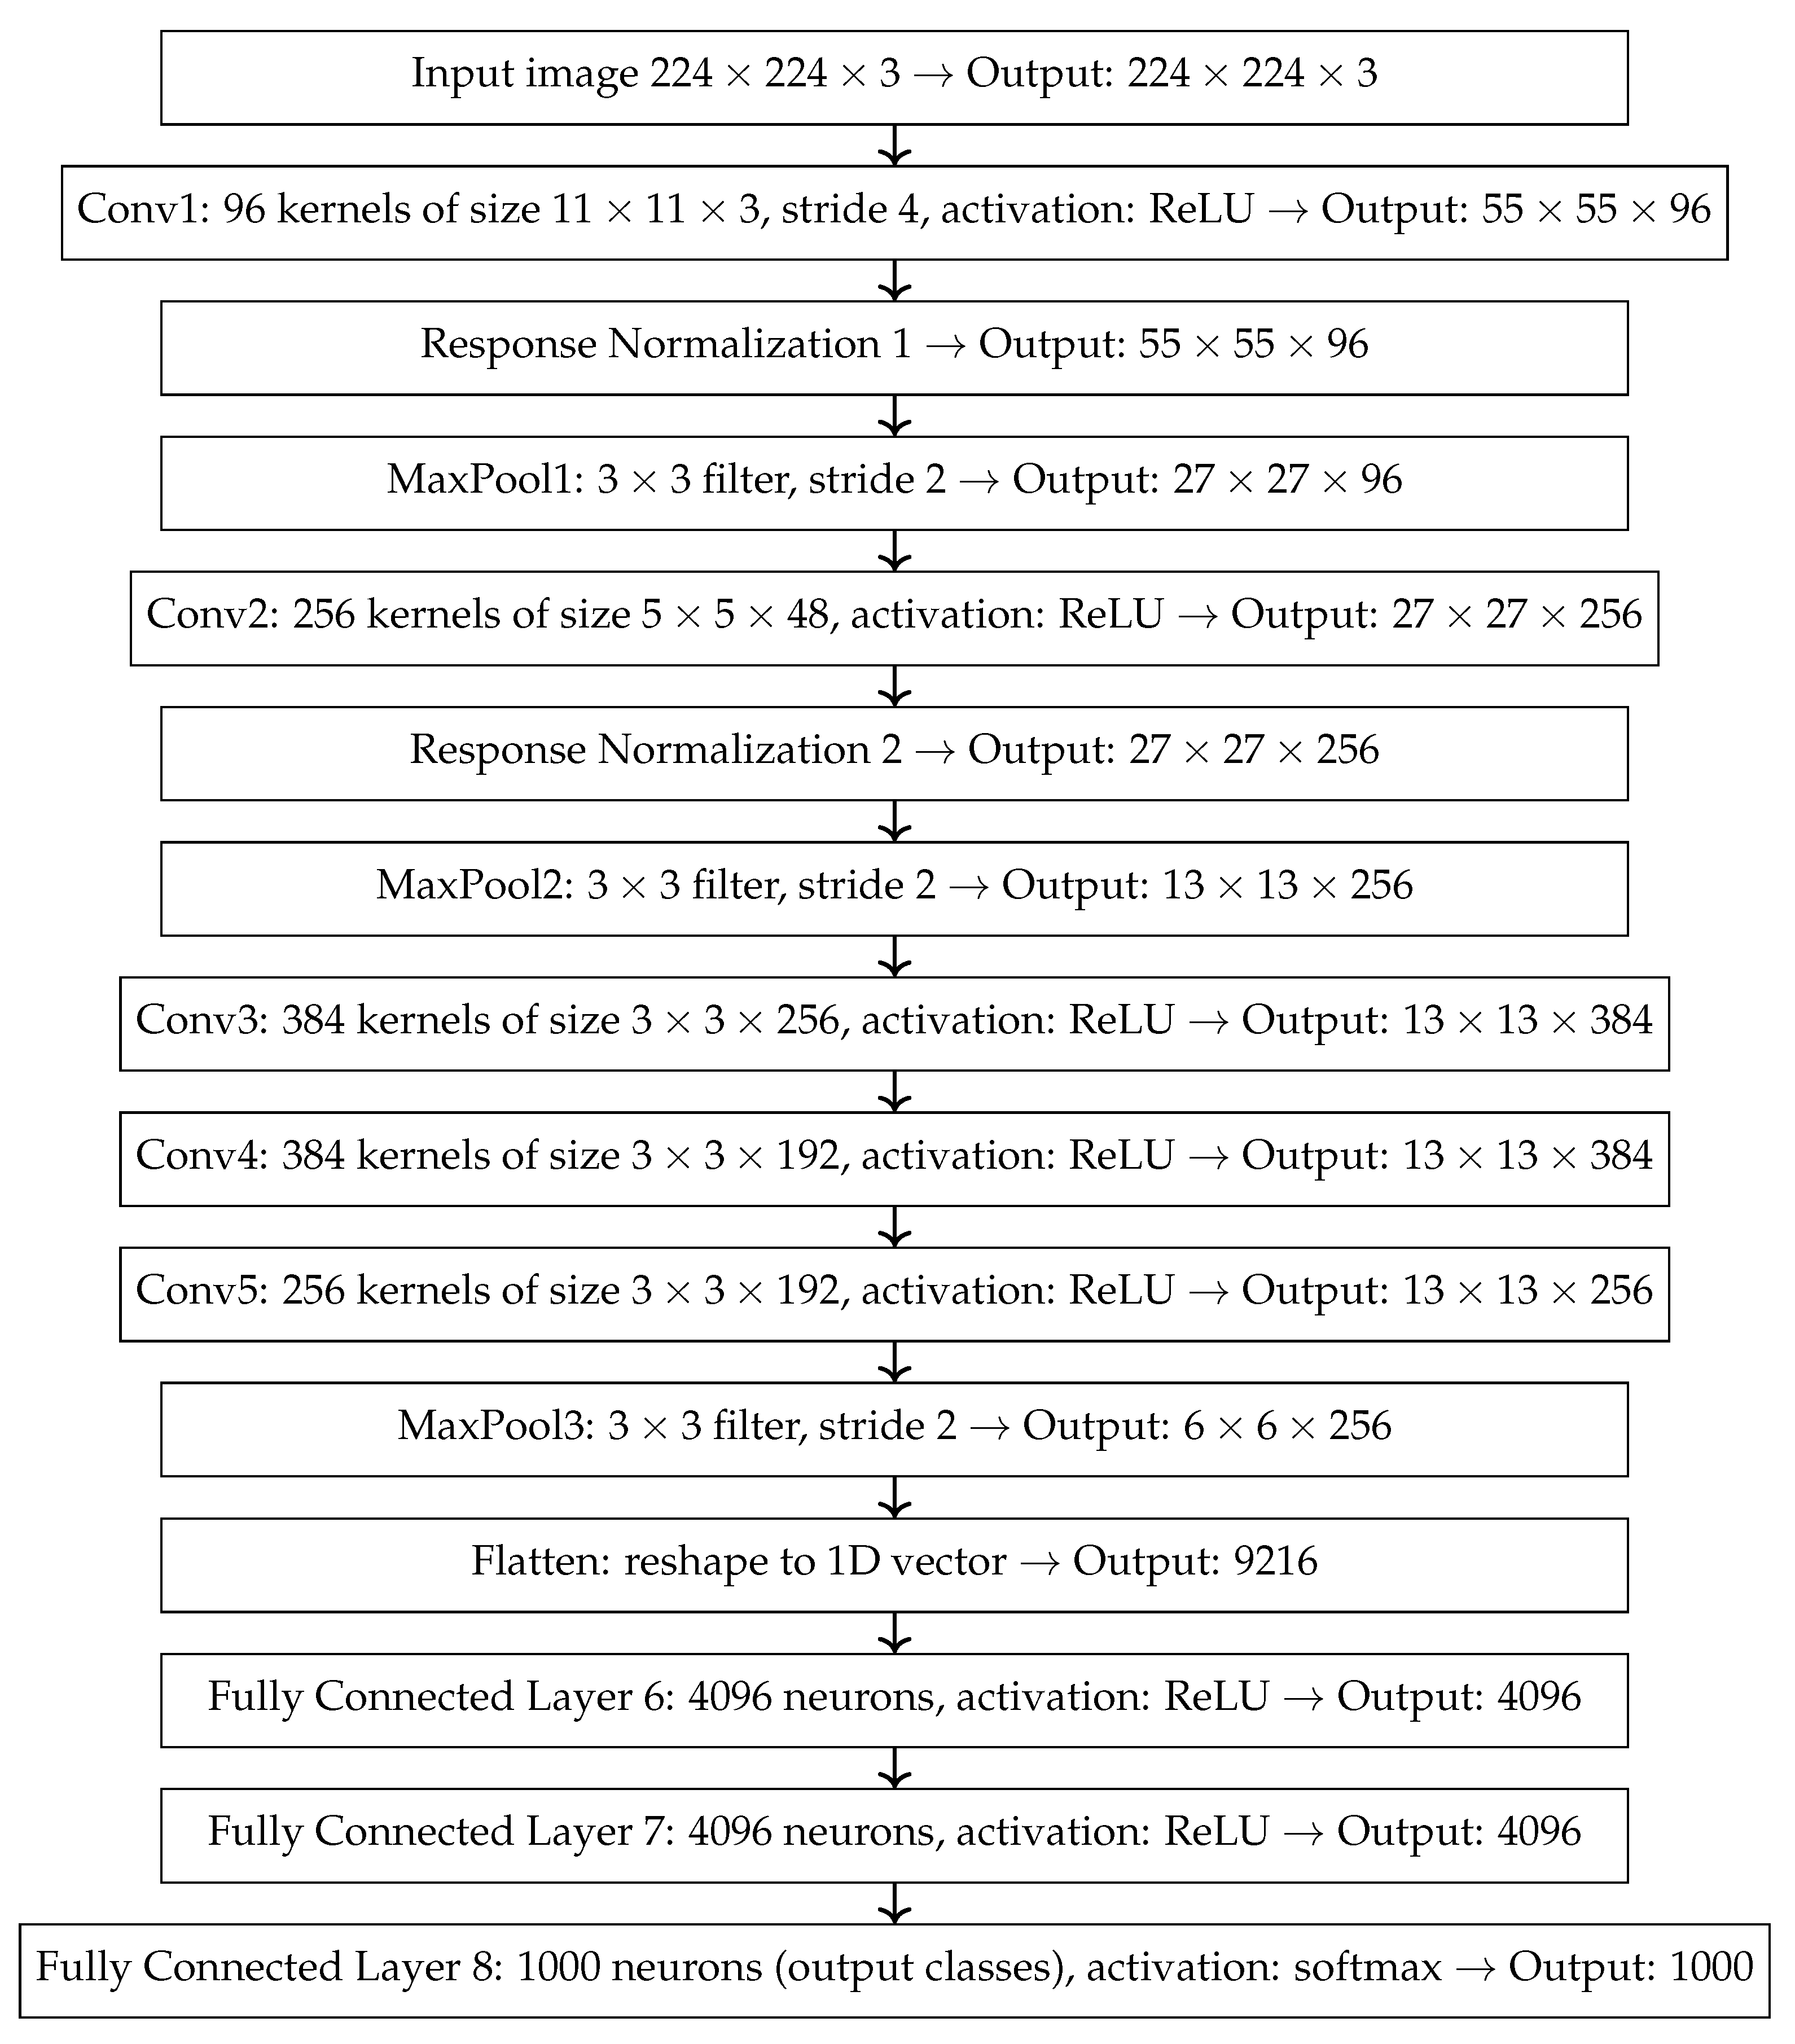
Figure A5.
A schematic diagram of the basic VGG architecture module.
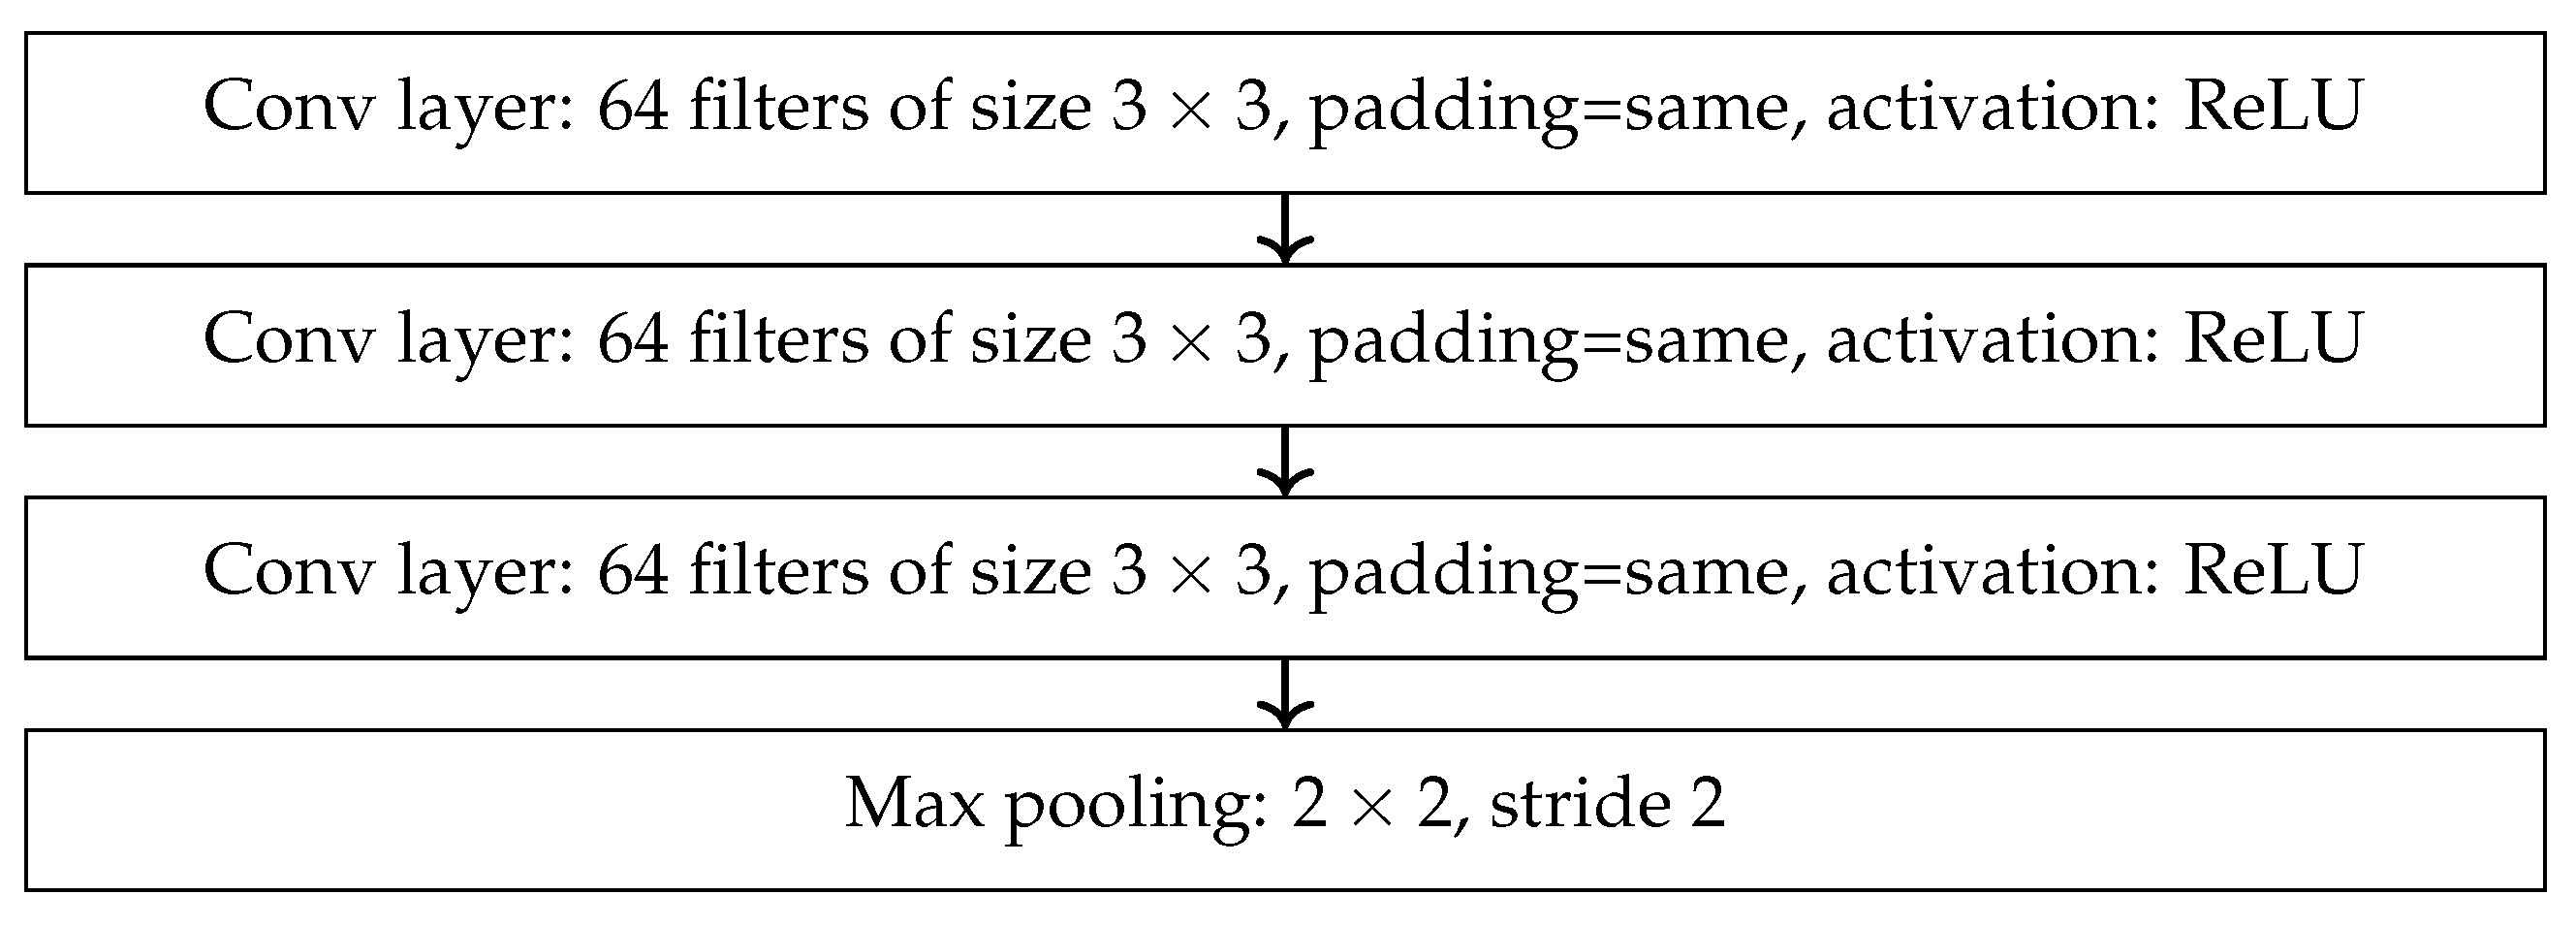
Figure A6.
A schematic diagram of the basic residual block in the ResNet architecture with skip connection.
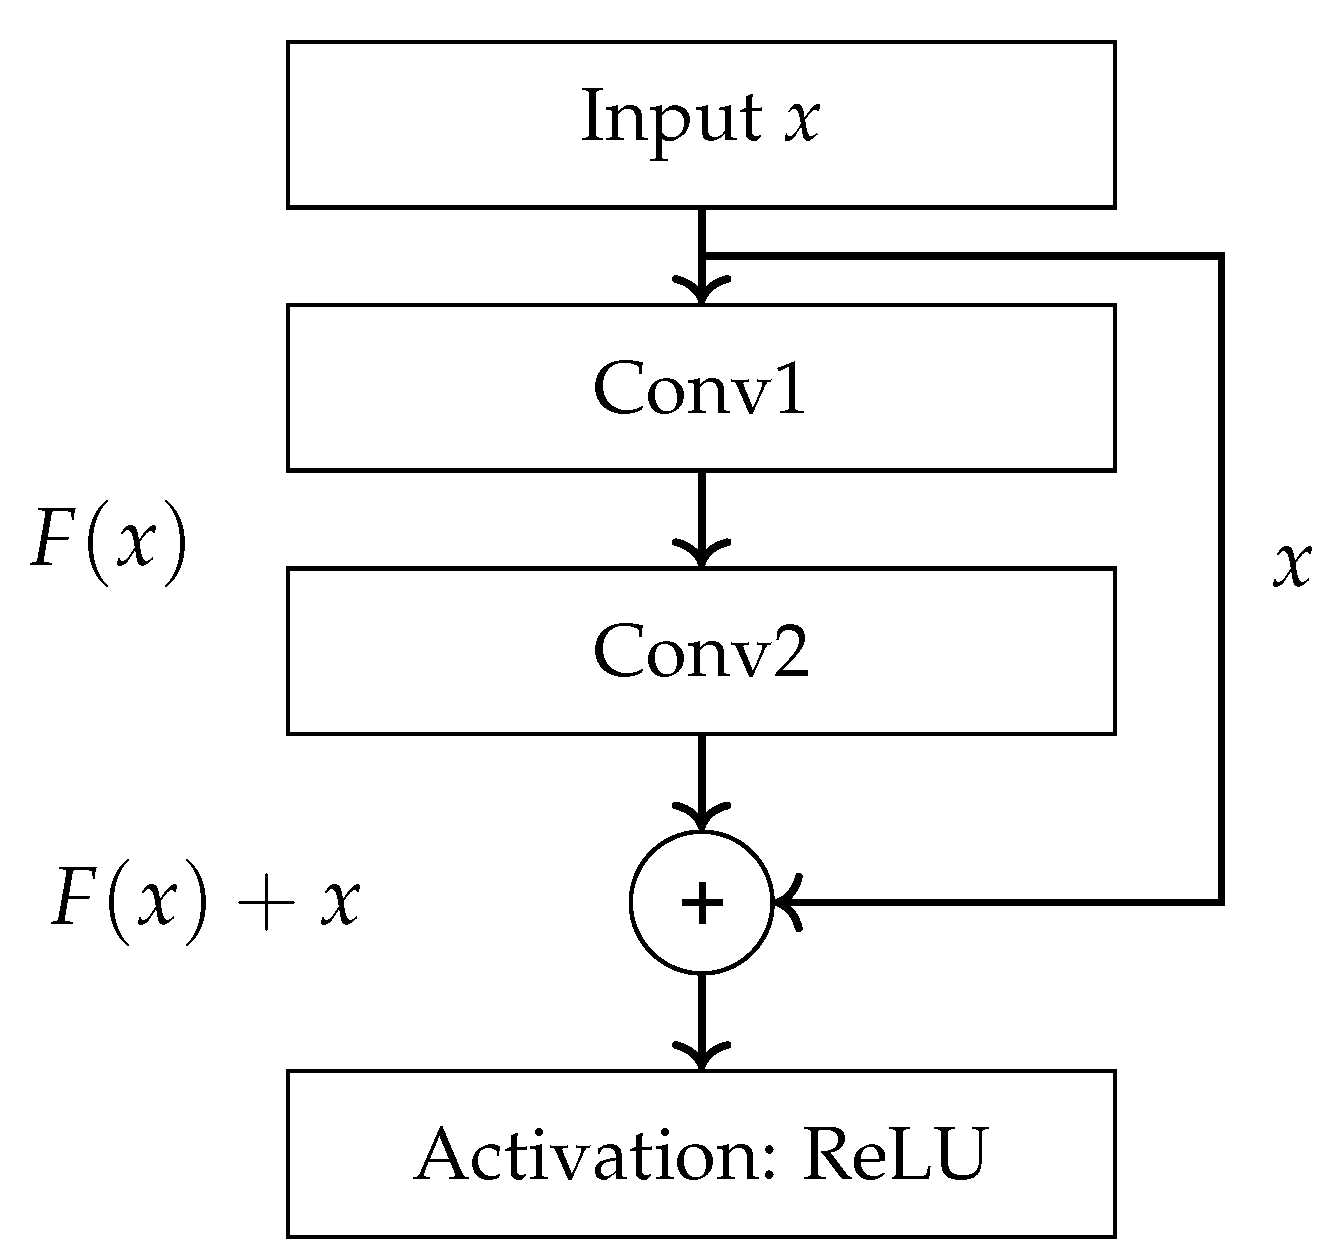
Figure A7.
A schematic diagram of the ResNeXt block: aggregated residual block with multiple parallel convolutional paths.
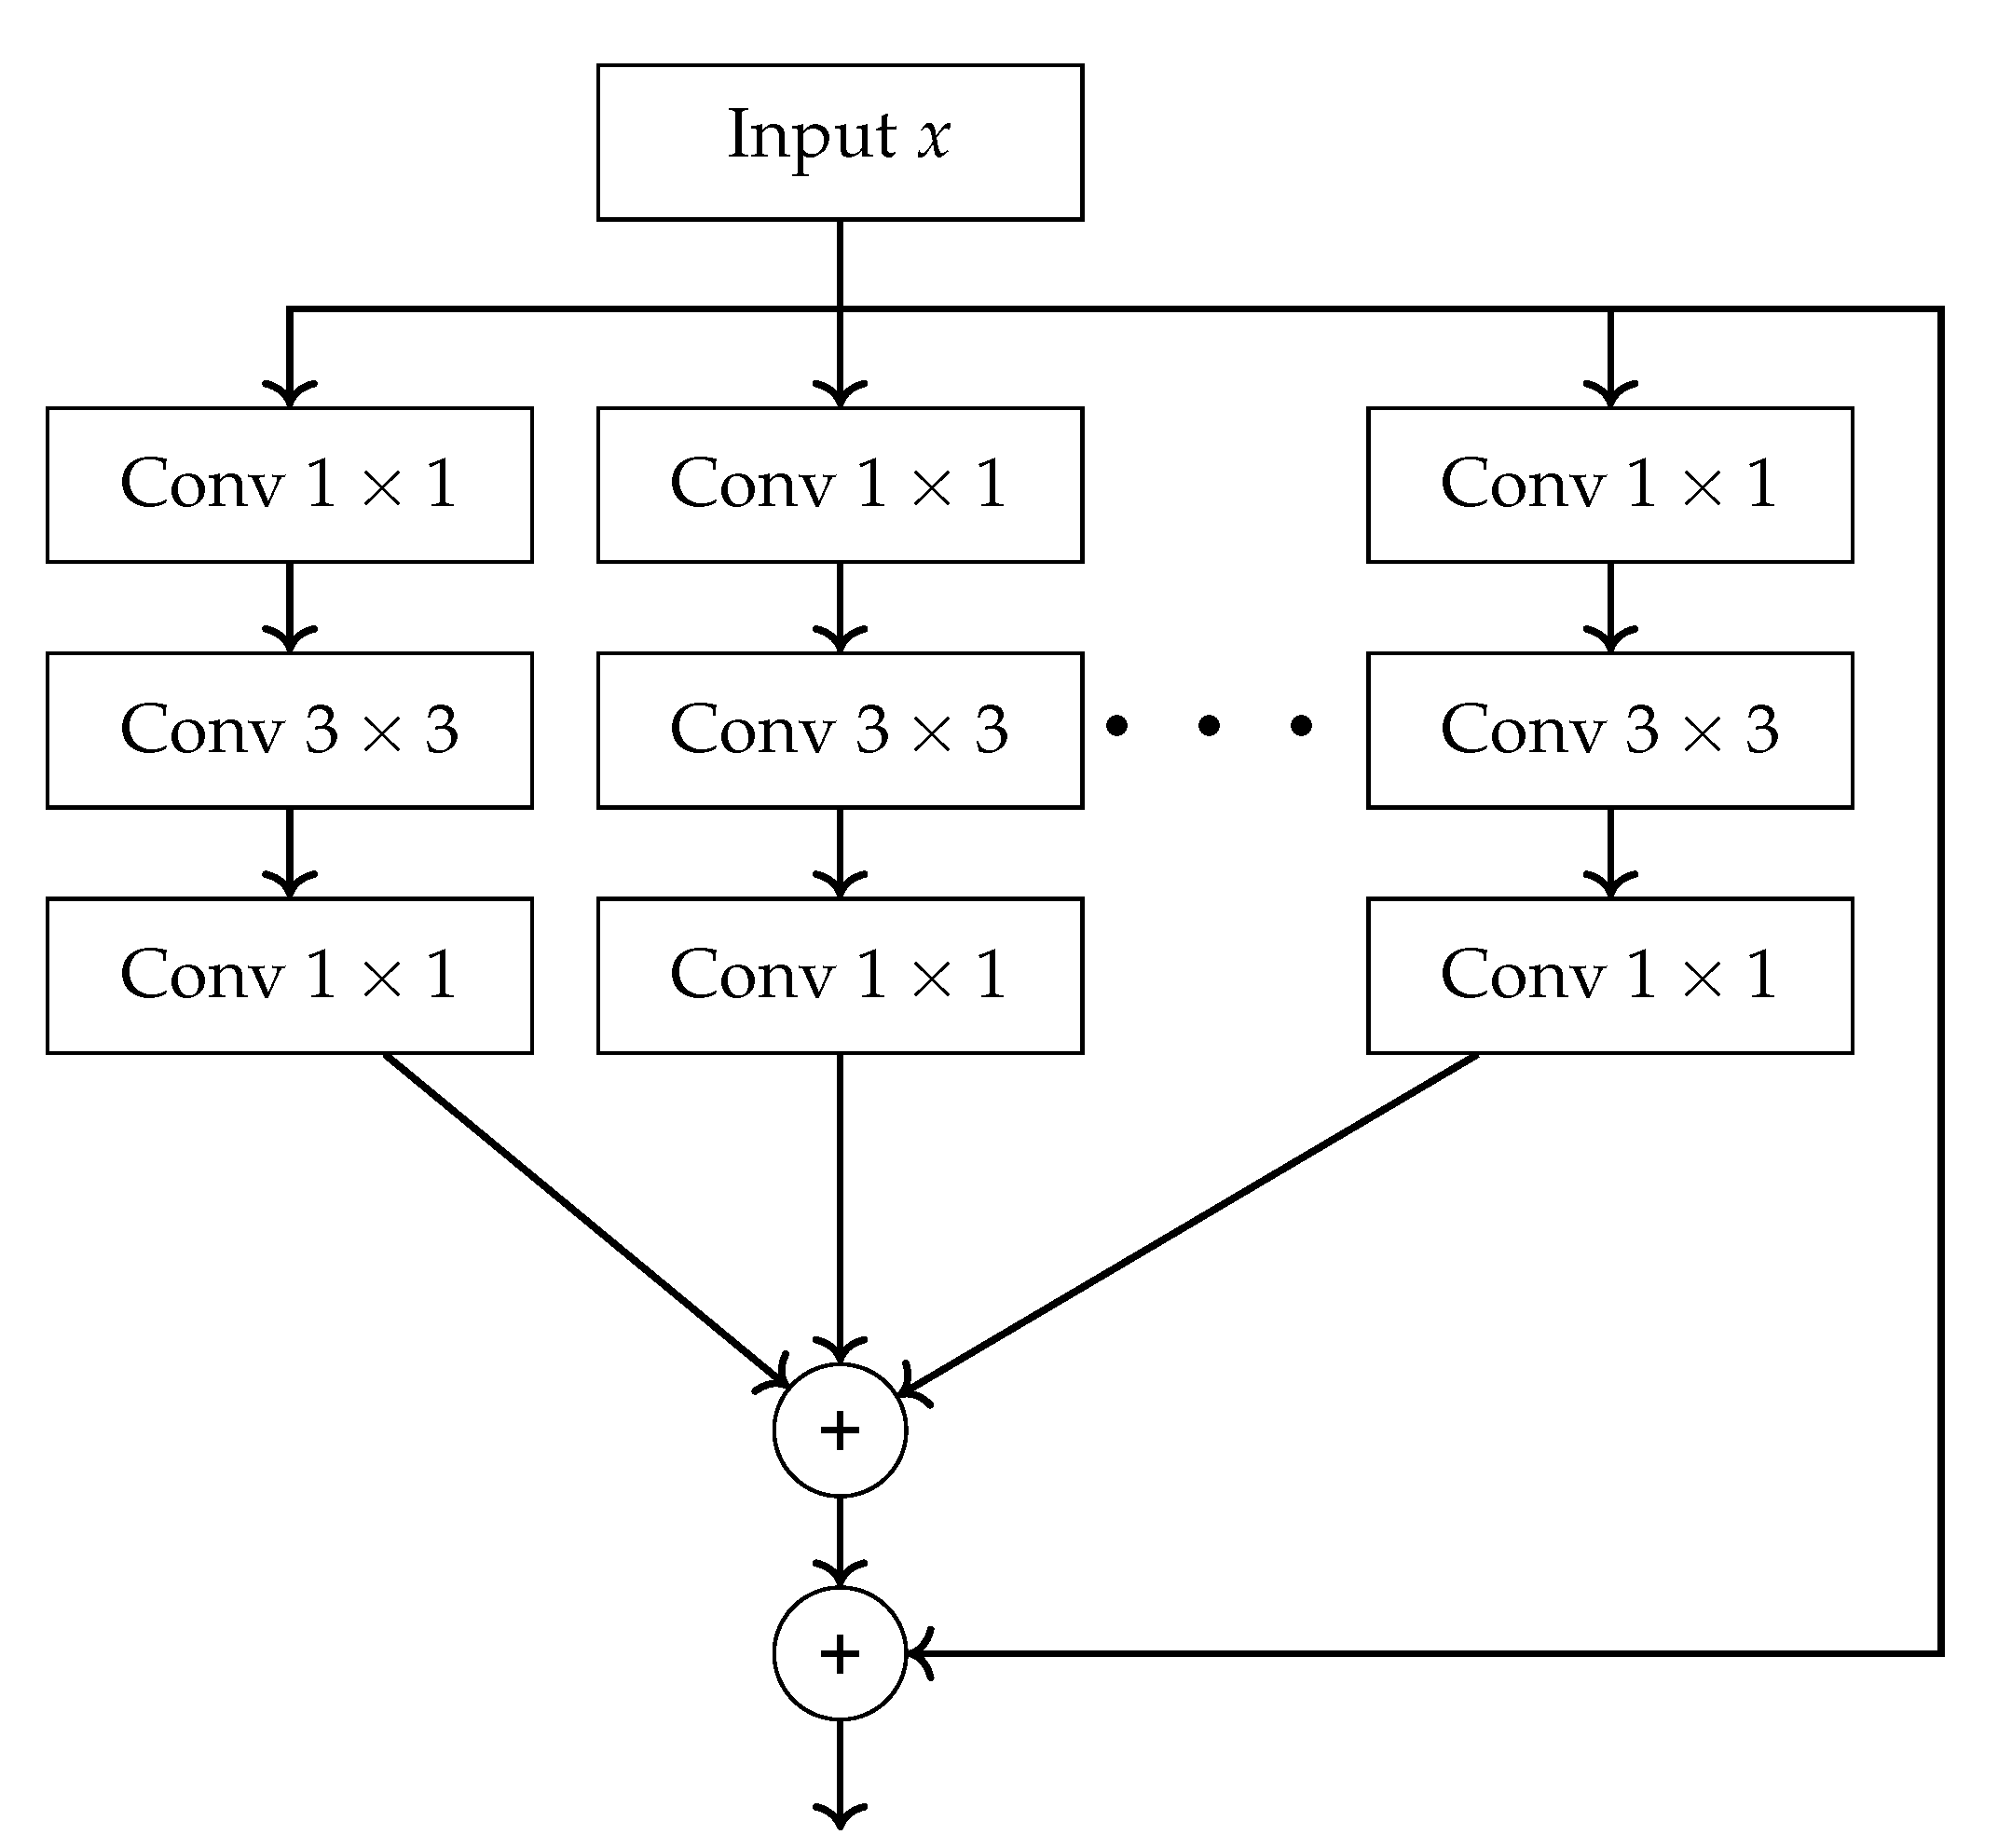
Figure A8.
A schematic diagram of the Inception module [88].
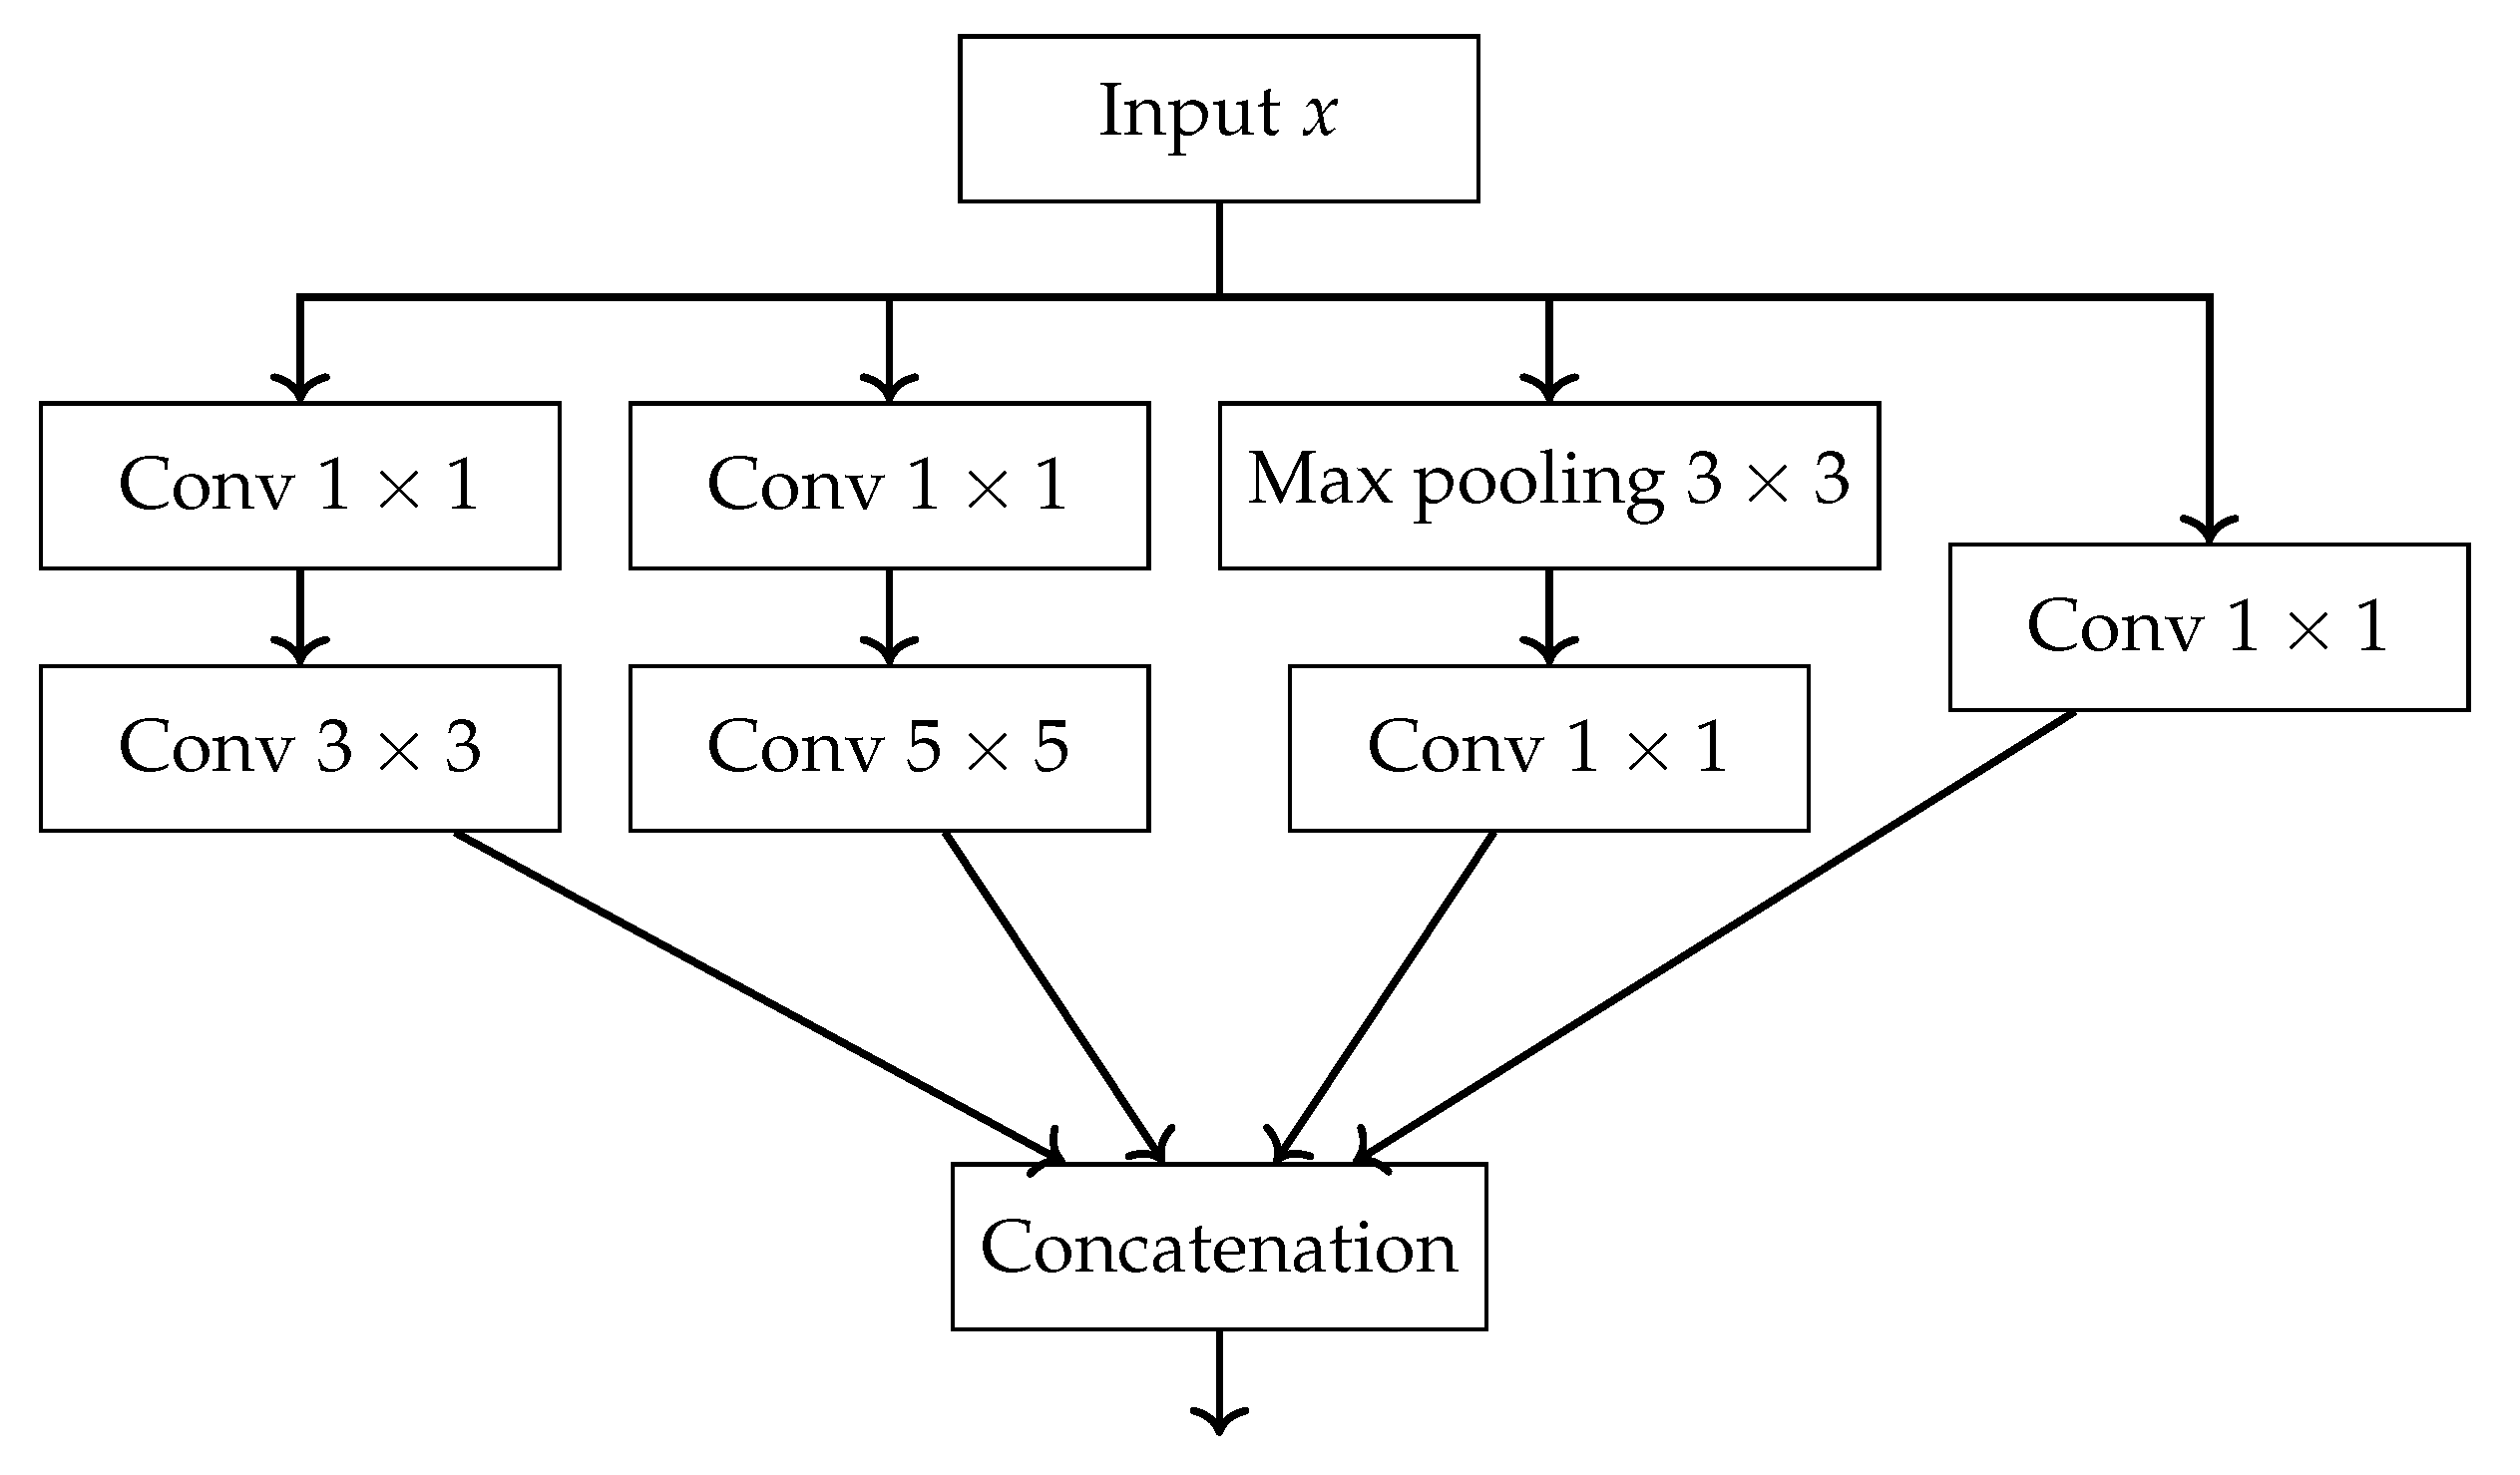
Figure A9.
A schematic diagram of the Xnception module.
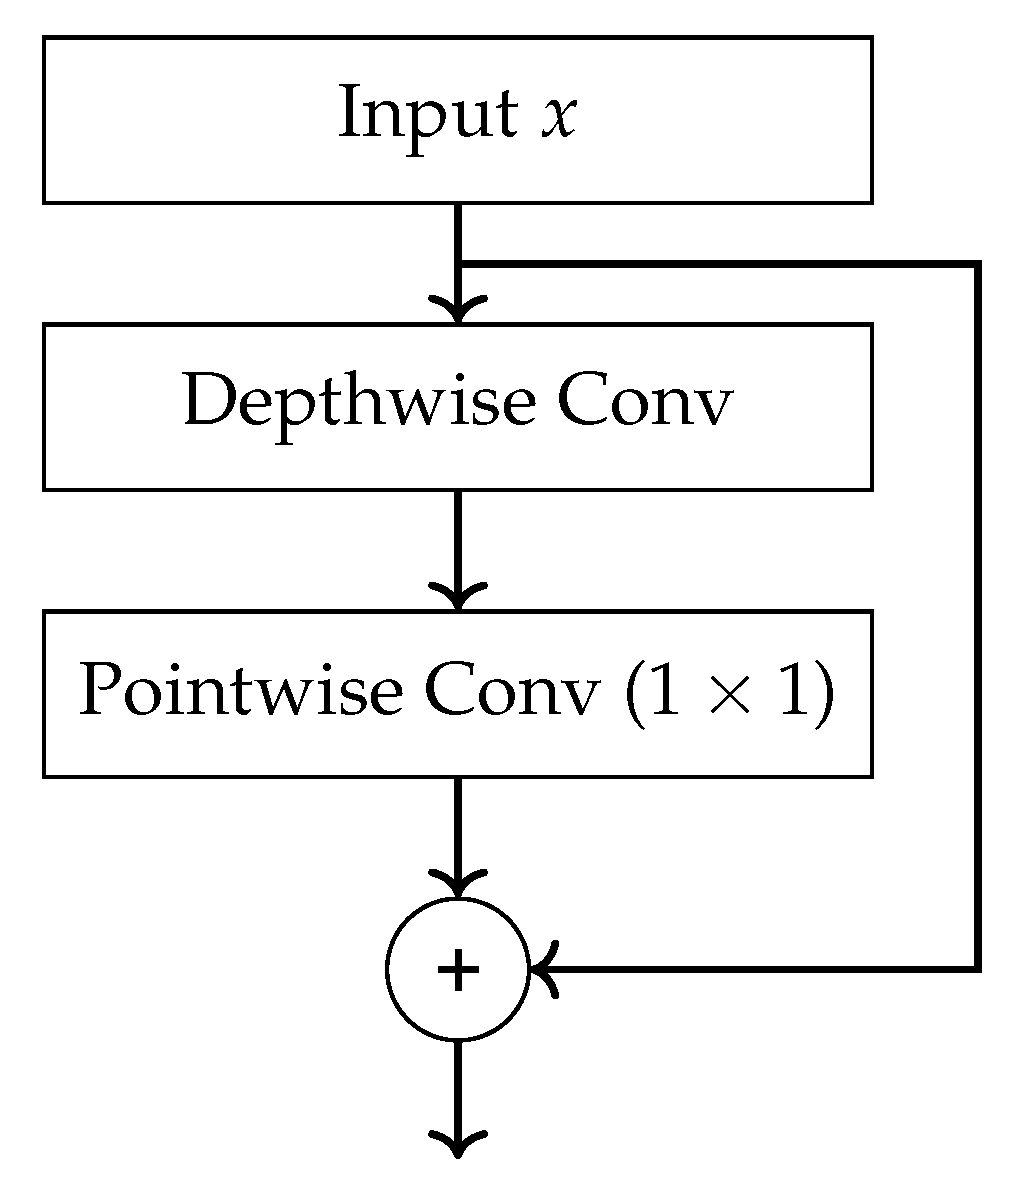
Figure A10.
PRISMA flow diagram.
References
- International Agency for Research on Cancer. Global Cancer Observatory: Cancer Today. 2024. Available online: https://gco.iarc.fr/today (accessed on 9 July 2025).
- Medycyna Praktyczna—Podręcznik Pediatrii. Epidemiologia. Zagadnienia ogóLne—Nowotwory Wieku Dziecięcego. Available online: https://www.mp.pl/podrecznik/pediatria/chapter/B42.71.13.1 (accessed on 9 July 2025).
- Siegel, R.L.; Giaquinto, A.N.; Jemal, A. Cancer statistics, 2024. CA A Cancer J. Clin. 2024, 74, 12–49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, N.; Wu, J.; Wang, Q.; Liang, Y.; Li, X.; Chen, G.; Ma, L.; Liu, X.; Zhou, F. Global burden of hematologic malignancies and evolution patterns over the past 30 years. Blood Cancer J. 2023, 13, 82. [Google Scholar] [CrossRef] [Scilit]
- Ross, M.H.; Pawlina, W. Histology: A Text and Atlas. With Correlated Cell and Molecular Biology; Lippincott Williams & Wilkins: Philadelphia, PA, USA, 2019; p. 314. [Google Scholar]
- Tsukasaki, K. Adult T-cell leukemia-lymphoma. Hematology 2012, 17, S32–S35. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Arber, D.A.; Orazi, A.; Hasserjian, R.P.; Borowitz, M.J.; Calvo, K.R.; Kvasnicka, H.M.; Wang, S.A.; Bagg, A.; Barbui, T.; Branford, S.; et al. International Consensus Classification of Myeloid Neoplasms and Acute Leukemias: Integrating morphologic, clinical, and genomic data. Blood 2022, 140, 1200–1228. [Google Scholar] [CrossRef] [Scilit]
- Mendez-Hernandez, A.; Moturi, K.; Hanson, V.; Andritsos, L.A. Hairy Cell Leukemia: Where Are We in 2023? Curr. Oncol. Rep. 2023, 25, 833–840. [Google Scholar] [CrossRef] [Scilit]
- Gutierrez, M.; Bladek, P.; Goksu, B.; Murga-Zamalloa, C.; Bixby, D.; Wilcox, R. T-Cell Prolymphocytic Leukemia: Diagnosis, Pathogenesis, and Treatment. Int. J. Mol. Sci. 2023, 24, 12106. [Google Scholar] [CrossRef] [Scilit]
- Drillet, G.; Pastoret, C.; Moignet, A.; Lamy, T.; Marchand, T. Large granular lymphocyte leukemia: An indolent clonal proliferative disease associated with an array of various immunologic disorders. Rev. Méd. Interne 2023, 44, 295–306. [Google Scholar] [CrossRef] [Scilit]
- George, B.S.; Yohannan, B.; Gonzalez, A.; Rios, A. Mixed-Phenotype Acute Leukemia: Clinical Diagnosis and Therapeutic Strategies. Biomedicines 2022, 10, 1974. [Google Scholar] [CrossRef] [Scilit]
- Bennett, J.M.; Catovsky, D.; Daniel, M.T.; Flandrin, G.; Galton, D.A.G.; Gralnick, H.R.; Sultan, C. Proposals for the Classification of the Acute Leukaemias French-American-British (FAB) Co-operative Group. Br. J. Haematol. 1976, 33, 451–458. [Google Scholar] [CrossRef] [Scilit]
- Ryan, M.M. Acute Promyelocytic Leukemia: A Summary. J. Adv. Pract. Oncol. 2018, 9, 178–187. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hallek, M.; Shanafelt, T.D.; Eichhorst, B. Seminar Chronic lymphocytic leukaemia. Lancet 2018, 391, 1524–1537. [Google Scholar] [CrossRef] [Scilit]
- Nagel, G.; Weber, D.; Fromm, E.; Erhardt, S.; Lübbert, M.; Fiedler, W.; Kindler, T.; Krauter, J.; Brossart, P.; Kündgen, A.; et al. Epidemiological, genetic, and clinical characterization by age of newly diagnosed acute myeloid leukemia based on an academic population-based registry study (AMLSG BiO). Ann. Hematol. 2017, 96, 1993–2003. [Google Scholar] [CrossRef] [Scilit]
- Puckett, Y.; Chan, O. Acute Lymphocytic Leukemia. In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2023. Available online: https://www.ncbi.nlm.nih.gov/books/NBK459149/ (accessed on 20 July 2025).
- American Cancer Society. Key Statistics for Chronic Myeloid Leukemia (CML). Available online: https://www.cancer.org/cancer/types/chronic-myeloid-leukemia/about/statistics.html (accessed on 20 July 2025).
- American Cancer Society. Key Statistics for Chronic Lymphocytic Leukemia (CLL). Available online: https://www.cancer.org/cancer/types/chronic-lymphocytic-leukemia/about/key-statistics.html (accessed on 20 July 2025).
- Park, S.; Park, Y.H.; Huh, J.; Baik, S.M.; Park, D.J. Deep learning model for differentiating acute myeloid and lymphoblastic leukemia in peripheral blood cell images via myeloblast and lymphoblast classification. Digit. Health 2024, 10, 1–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chiaretti, S.; Zini, G.; Bassan, R. Diagnosis and subclassification of acute lymphoblastic leukemia. Mediterr. J. Hematol. Infect. Dis. 2014, 6, e2014073. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Eden, R.E.; Coviello, J.M. Chronic Myelogenous Leukemia. In StatPearls; StatPearls Publishing: Treasure Island, FL, USA, 2023. Available online: https://www.ncbi.nlm.nih.gov/books/NBK531459/ (accessed on 20 July 2025).
- Penn Medicine. Chronic Myeloid Leukemia (CML). 2025. Available online: https://www.pennmedicine.org/conditions/chronic-myeloid-leukemia (accessed on 20 July 2025).
- Rai, K.R.; Sawitsky, A.; Cronkite, E.P.; Chanana, A.D.; Levy, R.N.; Pasternack, B.S. Clinical Staging of Chronic Lymphocytic Leukemia. Blood 1975, 46, 219–234. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zengin, N.; Kars, A.; Kansu, E.; Ozdemir, O.; Barista, I.; Gullu, I.; Guler, N.; Ozisik, Y.; Dundar, S.; Firat, D. Comparison of Rai and Binet classifications in chronic lymphocytic leukemia. Hematology 1997, 2, 125–129. [Google Scholar] [CrossRef] [Scilit]
- WHO Classification of Tumours Editorial Board. Haematolymphoid Tumours [Internet], 5th ed.; WHO Classification of Tumours Series; International Agency for Research on Cancer: Lyon, France, 2024; Volume 11, Available online: https://tumourclassification.iarc.who.int/chapters/63 (accessed on 20 July 2025).
- Matek, C.; Krappe, S.; Münzenmayer, C.; Haferlach, T.; Marr, C.; An Expert-Annotated Dataset of Bone Marrow Cytology in Hematologic Malignancies. The Cancer Imaging Archive. 2021. Available online: https://www.cancerimagingarchive.net/collection/bone-marrow-cytomorphology_mll_helmholtz_fraunhofer/ (accessed on 12 July 2025).
- Bain, B.J. Routine and specialised techniques in the diagnosis of haematological neoplasms. J. Clin. Pathol. 1995, 48, 501–508. [Google Scholar] [CrossRef] [Scilit]
- Dehkharghanian, T.; Mu, Y.; Tizhoosh, H.R.; Campbell, C.J. Applied machine learning in hematopathology. Int. J. Lab. Hematol. 2023, 45, 87–94. [Google Scholar] [CrossRef] [Scilit]
- Browman, G.P.; Neame, P.B.; Soamboonsrup, P. The Contribution of Cytochemistry and Immunophenotyping to the Reproducibility of the FAB Classification in Acute Leukemia. Blood 1986, 68, 900–905. [Google Scholar] [CrossRef] [Scilit]
- Eckardt, J.N.; Schmittmann, T.; Riechert, S.; Kramer, M.; Sulaiman, A.S.; Sockel, K.; Kroschinsky, F.; Schetelig, J.; Wagenführ, L.; Schuler, U.; et al. Deep learning identifies Acute Promyelocytic Leukemia in bone marrow smears. BMC Cancer 2022, 22, 201. [Google Scholar] [CrossRef] [Scilit]
- Karar, M.E.; Alotaibi, B.; Alotaibi, M. Intelligent Medical IoT-Enabled Automated Microscopic Image Diagnosis of Acute Blood Cancers. Sensors 2022, 22, 2348. [Google Scholar] [CrossRef] [Scilit]
- Rastogi, P.; Khanna, K.; Singh, V. LeuFeatx: Deep learning–based feature extractor for the diagnosis of acute leukemia from microscopic images of peripheral blood smear. Comput. Biol. Med. 2022, 142, 105236. [Google Scholar] [CrossRef] [Scilit]
- Musleh, S.; Islam, M.T.; Alam, M.T.; Househ, M.; Shah, Z.; Alam, T. ALLD: Acute Lymphoblastic Leukemia Detector; Studies in Health Technology and Informatics; IOS Press BV: Amsterdam, The Netherlands, 2022; Volume 289, pp. 77–80. [Google Scholar] [CrossRef] [Scilit]
- Jawahar, M.; Sharen, H.; Anbarasi, J.; Gandomi, A.H. ALNett: A cluster layer deep convolutional neural network for acute lymphoblastic leukemia classification. Comput. Biol. Med. 2022, 148, 105894. [Google Scholar] [CrossRef] [Scilit]
- Abunadi, I.; Senan, E.M. Multi-Method Diagnosis of Blood Microscopic Sample for Early Detection of Acute Lymphoblastic Leukemia Based on Deep Learning and Hybrid Techniques. Sensors 2022, 22, 1629. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manescu, P.; Narayanan, P.; Bendkowski, C.; Elmi, M.; Claveau, R.; Pawar, V.; Brown, B.J.; Shaw, M.; Rao, A.; Fernandez-Reyes, D. Detection of acute promyelocytic leukemia in peripheral blood and bone marrow with annotation-free deep learning. Sci. Rep. 2023, 13, 2562. [Google Scholar] [CrossRef] [Scilit]
- Ouyang, N.; Wang, W.; Ma, L.; Wang, Y.; Chen, Q.; Yang, S.; Xie, J.; Su, S.; Cheng, Y.; Cheng, Q.; et al. Diagnosing acute promyelocytic leukemia by using convolutional neural network. Clin. Chim. Acta 2021, 512, 1–6. [Google Scholar] [CrossRef] [Scilit]
- Osman, M.; Akkus, Z.; Jevremovic, D.; Nguyen, P.L.; Roh, D.; Al-Kali, A.; Patnaik, M.M.; Nanaa, A.; Rizk, S.; Salama, M.E. Classification of monocytes, promonocytes and monoblasts using deep neural network models: An area of unmet need in diagnostic hematopathology. J. Clin. Med. 2021, 10, 2264. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boldú, L.; Merino, A.; Acevedo, A.; Molina, A.; Rodellar, J. A deep learning model (ALNet) for the diagnosis of acute leukaemia lineage using peripheral blood cell images. Comput. Methods Programs Biomed. 2021, 202, 105999. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pałczyński, K.; Śmigiel, S.; Gackowska, M.; Ledziński, D.; Bujnowski, S.; Lutowski, Z. IoT application of transfer learning in hybrid artificial intelligence systems for acute lymphoblastic leukemia classification. Sensors 2021, 21, 8025. [Google Scholar] [CrossRef] [Scilit]
- Jiang, Z.; Dong, Z.; Wang, L.; Jiang, W. Method for Diagnosis of Acute Lymphoblastic Leukemia Based on ViT-CNN Ensemble Model. Comput. Intell. Neurosci. 2021, 7529893. [Google Scholar] [CrossRef] [Scilit]
- Chen, Y.M.; Chou, F.I.; Ho, W.H.; Tsai, J.T. Classifying microscopic images as acute lymphoblastic leukemia by Resnet ensemble model and Taguchi method. BMC Bioinform. 2021, 22, 615. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dese, K.; Raj, H.; Ayana, G.; Yemane, T.; Adissu, W.; Krishnamoorthy, J.; Kwa, T. Accurate Machine-Learning-Based classification of Leukemia from Blood Smear Images. Clin. Lymphoma Myeloma Leuk. 2021, 21, e903–e914. [Google Scholar] [CrossRef] [Scilit]
- Haferlach, T.; Pohlkamp, C.; Heo, I.; Drescher, R.; Hänselmann, S.; Lörch, T.; Kern, W.; Haferlach, C.; Nadarajah, N. Automated Peripheral Blood Cell Differentiation Using Artificial Intelligence—A Study with More Than 10,000 Routine Samples in a Specialized Leukemia Laboratory. Blood 2021, 138, 103. [Google Scholar] [CrossRef] [Scilit]
- Hussein, S.E.; Chen, P.; Medeiros, L.J.; Wistuba, I.I.; Jaffray, D.; Wu, J.; Khoury, J.D. Artificial intelligence strategy integrating morphologic and architectural biomarkers provides robust diagnostic accuracy for disease progression in chronic lymphocytic leukemia. J. Pathol. 2022, 256, 4–14. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, K.; Hu, J. Classification of acute myeloid leukemia M1 and M2 subtypes using machine learning. Comput. Biol. Med. 2022, 147, 105741. [Google Scholar] [CrossRef] [Scilit]
- Eckardt, J.N.; Middeke, J.; Riechert, S.; Schmittmann, T.; Sulaiman, A.; Kramer, M.; Sockel, K.; Kroschinsky, P.; Schuler, U.; Schetelig, J.; et al. Deep learning detects acute myeloid leukemia and predicts NPM1 mutation status from bone marrow smears. Leukemia 2022, 36, 111–118. [Google Scholar] [CrossRef] [Scilit]
- Wang, W.; Luo, M.; Guo, P.; Wei, Y.; Tan, Y.; Shi, H. Artificial intelligence-assisted diagnosis of hematologic diseases based on bone marrow smears using deep neural networks. Comput. Methods Programs Biomed. 2023, 231, 107343. [Google Scholar] [CrossRef] [Scilit]
- Abhishek, A.; Jha, R.K.; Sinha, R.; Jha, K. Automated detection and classification of leukemia on a subject-independent test dataset using deep transfer learning supported by Grad-CAM visualization. Biomed. Signal Process. Control 2023, 83, 104722. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Z.; Arabyarmohammadi, S.; Leo, P.; Meyerson, H.; Metheny, L.; Xu, J.; Madabhushi, A. Automatic myeloblast segmentation in acute myeloid leukemia images based on adversarial feature learning. Comput. Methods Programs Biomed. 2024, 243, 107852. [Google Scholar] [CrossRef] [Scilit]
- Xiao, Y.; Huang, Z.; Wu, J.; Zhang, Y.; Yang, Y.; Xu, C.; Guo, F.; Ni, X.; Hu, X.; Yang, J.; et al. Rapid screening of acute promyelocytic leukaemia in daily batch specimens: A novel artificial intelligence-enabled approach to bone marrow morphology. Clin. Transl. Med. 2024, 14, e1783. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, M.L.; Huang, Z.B. An ensemble-acute lymphoblastic leukemia model for acute lymphoblastic leukemia image classification. Math. Biosci. Eng. 2024, 21, 1959–1978. [Google Scholar] [CrossRef] [Scilit]
- Jawahar, M.; Anbarasi, L.J.; Narayanan, S.; Gandomi, A.H. An attention-based deep learning for acute lymphoblastic leukemia classification. Sci. Rep. 2024, 14, 17447. [Google Scholar] [CrossRef] [Scilit]
- Aby, A.E.; Salaji, S.; Anilkumar, K.K.; Rajan, T. Classification of acute myeloid leukemia by pre-trained deep neural networks: A comparison with different activation functions. Med. Eng. Phys. 2025, 135, 104277. [Google Scholar] [CrossRef] [Scilit]
- Mehan, V. Artificial Intelligence Powered Automated and Early Diagnosis of Acute Lymphoblastic Leukemia Cancer in Histopathological Images: A Robust SqueezeNet-Enhanced Machine Learning Framework. Int. J. Telemed. Appl. 2025, 2025, 2257215. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Labati, R.D.; Piuri, V.; Scotti, F. All-IDB: The acute lymphoblastic leukemia image database for image processing. In Proceedings of the 2011 18th IEEE International Conference on Image Processing, Brussels, Belgium, 11–14 September 2011; pp. 2045–2048. [Google Scholar]
- Fišer, K.; Sieger, T.; Schumich, A.; Wood, B.; Irving, J.; Mejstříková, E.; Dworzak, M.N. Detection and monitoring of normal and leukemic cell populations with hierarchical clustering of flow cytometry data. Cytom. Part A 2012, 81A, 25–34. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Agaian, S.; Madhukar, M.; Chronopoulos, A.T. Automated screening system for acute myelogenous leukemia detection in blood microscopic images. IEEE Syst. J. 2014, 8, 995–1004. [Google Scholar] [CrossRef] [Scilit]
- Putzu, L.; Caocci, G.; Ruberto, C.D. Leucocyte classification for leukaemia detection using image processing techniques. Artif. Intell. Med. 2014, 62, 179–191. [Google Scholar] [CrossRef] [Scilit]
- Neoh, S.C.; Srisukkham, W.; Zhang, L.; Todryk, S.; Greystoke, B.; Lim, C.P.; Hossain, M.A.; Aslam, N. An Intelligent Decision Support System for Leukaemia Diagnosis using Microscopic Blood Images OPEN. Nat. Publ. Group 2015, 5, 14938. [Google Scholar] [CrossRef] [Scilit]
- Rawat, J.; Singh, A.; Bhadauria, H.S.; Virmani, J. Computer Aided Diagnostic System for Detection of Leukemia Using Microscopic Images. Procedia Comput. Sci. 2015, 70, 748–756. [Google Scholar] [CrossRef] [Scilit]
- Kazemi, F.; Najafabadi, T.; Araabi, B. Automatic Recognition of Acute Myelogenous Leukemia in Blood Microscopic Images Using K-means Clustering and Support Vector Machine. J. Med. Signals Sens. 2016, 6, 183–193. [Google Scholar] [CrossRef] [Scilit]
- Bigorra, L.; Merino, A.; Alférez, S.; Rodellar, J. Feature Analysis and Automatic Identification of Leukemic Lineage Blast Cells and Reactive Lymphoid Cells from Peripheral Blood Cell Images. J. Clin. Lab. Anal. 2017, 31, e22024. [Google Scholar] [CrossRef] [Scilit]
- Rawat, J.; Singh, A.; Bhadauria, H.S.; Virmani, J.; Devgun, J.S. Classification of acute lymphoblastic leukaemia using hybrid hierarchical classifiers. Multimed. Tools Appl. 2017, 76, 19057–19085. [Google Scholar] [CrossRef] [Scilit]
- Mooney, P.T. Blood Cell Images. Kaggle Dataset. 2025. Available online: https://www.kaggle.com/datasets/paultimothymooney/blood-cells (accessed on 12 July 2025).
- Rehman, A.; Abbas, N.; Saba, T.; Rahman, S.I.u.; Mehmood, Z.; Kolivand, H. Classification of acute lymphoblastic leukemia using deep learning. Microsc. Res. Tech. 2018, 81, 1310–1317. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shafique, S.; Tehsin, S. Acute lymphoblastic leukemia detection and classification of its subtypes using pretrained deep convolutional neural networks. Technol. Cancer Res. Treat. 2018, 17, 1–7. [Google Scholar] [CrossRef] [Scilit]
- Khosla, E.; Ramesh, D. Phase classification of chronic myeloid leukemia using convolution neural networks. In Proceedings of the 4th IEEE International Conference on Recent Advances in Information Technology, RAIT 2018, Dhanbad, India, 15–17 March 2018; pp. 1–6. [Google Scholar] [CrossRef] [Scilit]
- Huang, F.; Guang, P.; Li, F.; Liu, X.; Zhang, W.; Huang, W.; Haque, N. AML, ALL, and CML classification and diagnosis based on bone marrow cell morphology combined with convolutional neural network: A STARD compliant diagnosis research. Medicine 2020, 99, E23154. [Google Scholar] [CrossRef] [Scilit]
- Chandradevan, R.; Aljudi, A.A.; Drumheller, B.R.; Kunananthaseelan, N.; Amgad, M.; Gutman, D.A.; Cooper, L.A.; Jaye, D.L. Machine-based detection and classification for bone marrow aspirate differential counts: Initial development focusing on nonneoplastic cells. Lab. Investig. 2020, 100, 98–109. [Google Scholar] [CrossRef] [Scilit]
- Kowalski, P.; Smyk, R. Comparison of thresholding algorithms for automatic overhead line detection procedure. Przegląd Elektrotechniczny 2022, 98, 149–155. [Google Scholar] [CrossRef] [Scilit]
- Salah, H.T.; Muhsen, I.N.; Salama, M.E.; Owaidah, T.; Hashmi, S.K. Machine learning applications in the diagnosis of leukemia: Current trends and future directions. Int. J. Lab. Hematol. 2019, 41, 717–725. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Boldú, L.; Merino, A.; Alférez, S.; Molina, A.; Acevedo, A.; Rodellar, J. Automatic recognition of different types of acute leukaemia in peripheral blood by Image Analysis. J. Clin. Pathol. 2019, 72, 755–761. [Google Scholar] [CrossRef] [Scilit]
- Reta, C.; Altamirano, L.; Gonzalez, J.A.; Diaz-Hernandez, R.; Peregrina, H.; Olmos, I.; Alonso, J.E.; Lobato, R. Segmentation and classification of bone marrow cells images using contextual information for medical diagnosis of acute leukemias. PLoS ONE 2015, 10, e0130805. [Google Scholar]
- Bhattacharjee, R.; Saini, L.M. Robust technique for the detection of Acute Lymphoblastic Leukemia. In Proceedings of the 2015 IEEE Power, Communication and Information Technology Conference (PCITC), Bhubaneswar, India, 15–17 October 2015; pp. 657–662. [Google Scholar] [CrossRef] [Scilit]
- Shalev-Shwartz, S.; Ben-David, S. Understanding Machine Learning: From Theory to Algorithms; Cambridge University Press: Cambridge, UK, 2014. [Google Scholar]
- Breiman, L. Random forests. Mach. Learn. 2001, 45, 5–32. [Google Scholar] [CrossRef] [Scilit]
- Lloyd, S. Least squares quantization in PCM. IEEE Trans. Inf. Theory 1982, 28, 129–137. [Google Scholar] [CrossRef] [Scilit]
- Mantri, R.; Khan, R.A.H.; Mane, D.T. An Efficient System for Detection and Classification of Acute Lymphoblastic Leukemia Using Semi-Supervised Segmentation Technique. Int. Res. J. Multidiscip. Technovation 2025, 7, 121–134. [Google Scholar] [CrossRef] [Scilit]
- Matek, C.; Schwarz, S.; Spiekermann, K.; Marr, C. Human-level recognition of blast cells in acute myeloid leukaemia with Convolutional Neural Networks. Nat. Mach. Intell. 2019, 1, 538–544. [Google Scholar] [CrossRef] [Scilit]
- Cortes, C.; Vapnik, V. Support-vector networks. Mach. Learn. 1995, 20, 273–297. [Google Scholar] [CrossRef] [Scilit]
- LeCun, Y.; Bottou, L.; Bengio, Y.; Haffner, P. Gradient-based learning applied to document recognition. Proc. IEEE 1998, 86, 2278–2324. [Google Scholar] [CrossRef] [Scilit]
- Krizhevsky, A.; Sutskever, I.; Hinton, G.E. ImageNet classification with deep convolutional neural networks. Adv. Neural Inf. Process. Syst. 2017, 60, 84–90. [Google Scholar] [CrossRef] [Scilit]
- Simonyan, K.; Zisserman, A. Very deep convolutional networks for large-scale image recognition. arXiv 2014, arXiv:1409.1556. [Google Scholar]
- He, K.; Zhang, X.; Ren, S.; Sun, J. Deep residual learning for image recognition. In Proceedings of the IEEE Conference on Computer Vision and Pattern Recognition, Las Vegas, NV, USA, 27–30 June 2016; pp. 770–778. [Google Scholar]
- Xie, S.; Girshick, R.; Dollár, P.; Tu, Z.; He, K. Aggregated residual transformations for deep neural networks. In Proceedings of the IEEE Conference on Computer Vision and Pattern Recognition, Honolulu, HI, USA, 21–26 July 2017; pp. 1492–1500. [Google Scholar]
- Huang, G.; Liu, Z.; Van Der Maaten, L.; Weinberger, K.Q. Densely connected convolutional networks. In Proceedings of the IEEE Conference on Computer Vision and Pattern Recognition, Honolulu, HI, USA, 21–26 July 2017; pp. 4700–4708. [Google Scholar]
- Szegedy, C.; Liu, W.; Jia, Y.; Sermanet, P.; Reed, S.; Anguelov, D.; Erhan, D.; Vanhoucke, V.; Rabinovich, A. Going deeper with convolutions. In Proceedings of the IEEE Conference on Computer Vision and Pattern Recognition, Boston, MA, USA, 7–12 June 2015; pp. 1–9. [Google Scholar]
- Chollet, F. Xception: Deep learning with depthwise separable convolutions. In Proceedings of the IEEE Conference on Computer Vision and Pattern Recognition, Honolulu, HI, USA, 21–26 July 2017; pp. 1251–1258. [Google Scholar]
- Rolls, G. An Introduction to Specimen Processing. 2019. Available online: https://www.leicabiosystems.com/knowledge-pathway/an-introduction-to-specimen-processing/ (accessed on 22 July 2025).
- Taqi, S.A.; Sami, S.A.; Sami, L.B.; Zaki, S.A. A review of artifacts in histopathology. J. Oral Maxillofac. Pathol. 2018, 22, 279. [Google Scholar] [CrossRef] [Scilit]
- Patel, A.; Balis, U.G.; Cheng, J.; Li, Z.; Lujan, G.; Mcclintock, D.S.; Pantanowitz, L.; Parwani, A. Contemporary whole slide imaging devices and their applications within the modern pathology department: A selected hardware review. J. Pathol. Inform. 2021, 12, 50. [Google Scholar] [CrossRef] [Scilit]
- Basak, K.; Ozyoruk, K.B.; Demir, D. Whole Slide Images in Artificial Intelligence Applications in Digital Pathology: Challenges and Pitfalls. Turk. J. Pathol. 2023, 39, 101–108. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sellaro, T.L.; Filkins, R.; Hoffman, C.; Fine, J.L.; Ho, J.; Parwani, A.V.; Pantanowitz, L.; Montalto, M. Relationship between magnification and resolution in digital pathology systems. J. Pathol. Inform. 2013, 4, 21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nordin, N.; Rahim, S.N.A.; Omar, W.F.A.W.; Zulkarnain, S.; Sinha, S.; Kumar, S.; Haque, M. Preanalytical Errors in Clinical Laboratory Testing at a Glance: Source and Control Measures. Cureus 2024, 16, e57243. [Google Scholar] [CrossRef] [Scilit]
- Nakhleh, R.E.; Idowu, M.O.; Souers, R.J.; Meier, F.A.; Bekeris, L.G. Mislabeling of Cases, Specimens, Blocks, and Slides A College of American Pathologists Study of 136 Institutions. Arch. Pathol. Lab. Med. 2011, 135, 969–974. [Google Scholar] [CrossRef] [Scilit]
- Packer, M.D.C.; Ravinsky, E.; Azordegan, N. Patterns of Error in Interpretive Pathology: A Review of 23 PowerPoint Presentations of Discordances. Am. J. Clin. Pathol. 2021, 157, 767–773. [Google Scholar] [CrossRef] [Scilit]
- Dehan, L.M.; Lewis, J.S.; Mehrad, M.; Ely, K.A. Patterns of Major Frozen Section Interpretation Error: An In-Depth Analysis From a Complex Academic Surgical Pathology Practice. Am. J. Clin. Pathol. 2023, 160, 247–254. [Google Scholar] [CrossRef] [Scilit]
- Ministerstwo Zdrowia Rzeczypospolitej Polskiej. Rozporządzenie Ministra Zdrowia z Dnia 18 Grudnia 2017 r. w Sprawie Standardów Organizacyjnych Opieki Zdrowotnej w Dziedzinie Patomorfologii. Dziennik Ustaw Rzeczypospolitej Polskiej, poz. 2435/2017, Dz.U. 2017 poz. 2435. 2017. Available online: https://isap.sejm.gov.pl/isap.nsf/DocDetails.xsp?id=WDU20170002435 (accessed on 22 July 2025).
- Mutter, G.L.; Milstone, D.S.; Hwang, D.H.; Siegmund, S.; Bruce, A. Measuring digital pathology throughput and tissue dropouts. J. Pathol. Inform. 2022, 13, 100170. [Google Scholar] [CrossRef] [Scilit]
- Rao, G.G.; Crook, M.; Tillyer, M.L. Pathology tests: Is the time for demand management ripe at last? J. Clin. Pathol. 2003, 56, 243–248. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Feng, C.; Liu, F. Artificial intelligence in renal pathology: Current status and future. Biomol. Biomed. 2023, 23, 225–234. [Google Scholar] [CrossRef] [Scilit]
- Neto, P.C.; Montezuma, D.; Oliveira, S.P.; Oliveira, D.; Fraga, J.; Monteiro, A.; Monteiro, J.; Ribeiro, L.; Gonçalves, S.; Reinhard, S.; et al. An interpretable machine learning system for colorectal cancer diagnosis from pathology slides. NPJ Precis. Oncol. 2024, 8, 56. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- da Silva, L.M.; Pereira, E.M.; Salles, P.G.; Godrich, R.; Ceballos, R.; Kunz, J.D.; Casson, A.; Viret, J.; Chandarlapaty, S.; Ferreira, C.G.; et al. Independent real-world application of a clinical-grade automated prostate cancer detection system. J. Pathol. 2021, 254, 147–158. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Food and Drug Administration. Artificial Intelligence and Machine Learning (AI/ML)-Enabled Medical Devices. 2024. Available online: https://www.fda.gov/medical-devices/software-medical-device-samd/artificial-intelligence-and-machine-learning-aiml-enabled-medical-devices (accessed on 20 July 2025).
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.J.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMAScR): Checklist and Explanation. Ann. Intern. Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).