


Abstract
Streptococcus pneumoniae causes serious illnesses, such as pneumonia, bacteremia, and meningitis, mainly in immunocompromised individuals and those of extreme ages. Currently, pneumococcal conjugate vaccines (PCVs) are the best allies against pneumococcal diseases. In Brazil, the 10-valent and 13-valent PCVs have been available since 2010, but the threat of antimicrobial resistance persists and has been changing over time. We conducted a systematic review of the literature with works published since 2000, generating a parallel between susceptibility data on isolates recovered from colonization and invasive diseases before and after the implementation of PCVs for routine childhood use in Brazil. This systematic review was based on the Cochrane Handbook for Systematic Reviews of Interventions and Preferred Reporting Items for Systematic Literature Reviews and Meta-Analyses (PRISMA) guidelines. Despite the inclusion of PCVs at a large scale in the national territory, high frequencies of non-susceptibility to important drugs used in pneumococcal diseases are still observed, especially penicillin, as well as increasing resistance to macrolides. However, there are still drugs for which pneumococci have a comprehensive sensitivity profile.
1. Introduction
Streptococcus pneumoniae is a common colonizer of the human upper respiratory tract. However, pneumococci can cause milder diseases, such as acute otitis media (AOM) and sinusitis, as well as severe diseases, including community-acquired pneumonia (CAP), bacteremia, and meningitis, affecting individuals of all age groups, especially those of extremes ages and immunocompromised people [1,2,3,4].
The main prevention strategy against pneumococcal diseases is pneumococcal conjugate vaccines (PCVs). They confer a high degree of protection against specific serotypes, interfering in the fluctuation of their distribution and in the prevalence of resistance to antimicrobial agents [5,6]. There are several PCVs approved for use in children and adults in different countries [7,8,9,10,11,12,13]. In Brazil, the 7-valent PCV (PCV7; serotypes 4, 6B, 9V, 14,18C, 19F, and 23F) was initially made available, in 2001, in private immunization clinics for children and in the Brazilian public health system (Sistema Único de Saúde, SUS) for children < 5 years old who were at high risk of invasive pneumococcal diseases (IPD). In 2010, the 10-valent PCV (PCV10; PCV7 serotypes + 1, 5, and 7F) was introduced into the Brazilian National Immunization Program (NIP) for free-of-charge immunization of all children < 5 years old. Initially, the PCV10 schedule comprised three primary doses at 2, 4, and 6 months of age and a booster dose at 12–15 months of age (3p + 1), but, since 2016, the PCV10 dosing regimen in the Brazilian NIP changed to 2p + 1 (at 2 and 4 months of age and a booster dose at 12 months of age). In 2010, the 13-valent PCV (PCV13; PCV10 serotypes + 3, 6A, and 19A) replaced PCV7 in private clinics, and it was made available via SUS in 2019 for individuals aged 5 years or older who are at the highest risk for IPD, including patients living with HIV/AIDS, patients with cancer, and those who underwent solid organ or bone marrow transplantations. In 2023, the PCV15 (PCV13 serotypes + 22F and 33F) was approved for use in Brazil [13,14,15,16,17,18,19].
Although not compulsory, vaccination in Brazil is strongly recommended. The most used antipneumococcal vaccine in Brazil is PCV10, and between 2011 and 2022, considering the different geographical regions, the average PCV10 vaccination coverage with primary doses and the booster dose was 88.5% and 80.6%, respectively. Data on PCV13 coverage are limited, but a few studies report a low coverage (<8%) among children < 5 years old [20,21,22].
Some post-PCV10 introduction studies in Brazil indicate a reduction in the average mortality rate of pneumonia (11%; from 29.69 to 23.40 per 100,000) in children younger than 1 year after four years of vaccination [23] and a significant reduction, between 13.9% and 17.6%, in hospitalizations for pneumonia in the target groups of vaccination over five years after PCV10 implementation [24]. On the other hand, the incidence of pneumococcal meningitis remains high in Brazil, with approximately 1000 cases/year [25].
Beta-lactams, especially penicillin and amoxicillin, are the main, but not exclusive, choices to treat pneumococcal diseases. Other antimicrobial agents frequently used against pneumococcal diseases include macrolides, fluoroquinolones, and lincosamides [26,27,28]. The first choice for AOM is amoxicillin, which may be combined with clavulanate in cases of recurrence within 30 days or when associated with other symptoms. For allergic people, cefdinir or azithromycin has been frequently prescribed [29]. For CAP patients without comorbidities, the most indicated treatment includes amoxicillin, doxycycline, or a macrolide, and for those with comorbidity, a fluoroquinolone or a combination of amoxicillin with clavulanate or cephalosporin plus a macrolide or doxycycline. Furthermore, for patients admitted to a hospital, a fluoroquinolone in monotherapy or the combination of a macrolide with a beta-lactam is recommended, with a difference in treatment for patients in intensive care, who require the combination of a beta-lactam with a macrolide or a fluoroquinolone [30].
Antimicrobial resistance, however, is a concern among S. pneumoniae. Penicillin non-susceptible pneumococci (PNSP) are considered a medium priority risk to human health by the World Health Organization [31]. Drug-resistant S. pneumoniae is also classified as a serious threat in the USA [32]. The growing report of resistance to different antimicrobial agents has been a cause for concern in public health and demands strategies in public policies, as well as therapeutic alternatives [27].
This systematic literature review aims to verify the Brazilian scenario pre- and post-PCV10 regarding antimicrobial resistance among S. pneumoniae isolates associated with colonization and diseases recovered from individuals from all age groups. For this reason, we selected the year 2000 as a starting point, considering that it corresponds to 10 years before the introduction of PCV10 in Brazil.
2. Results
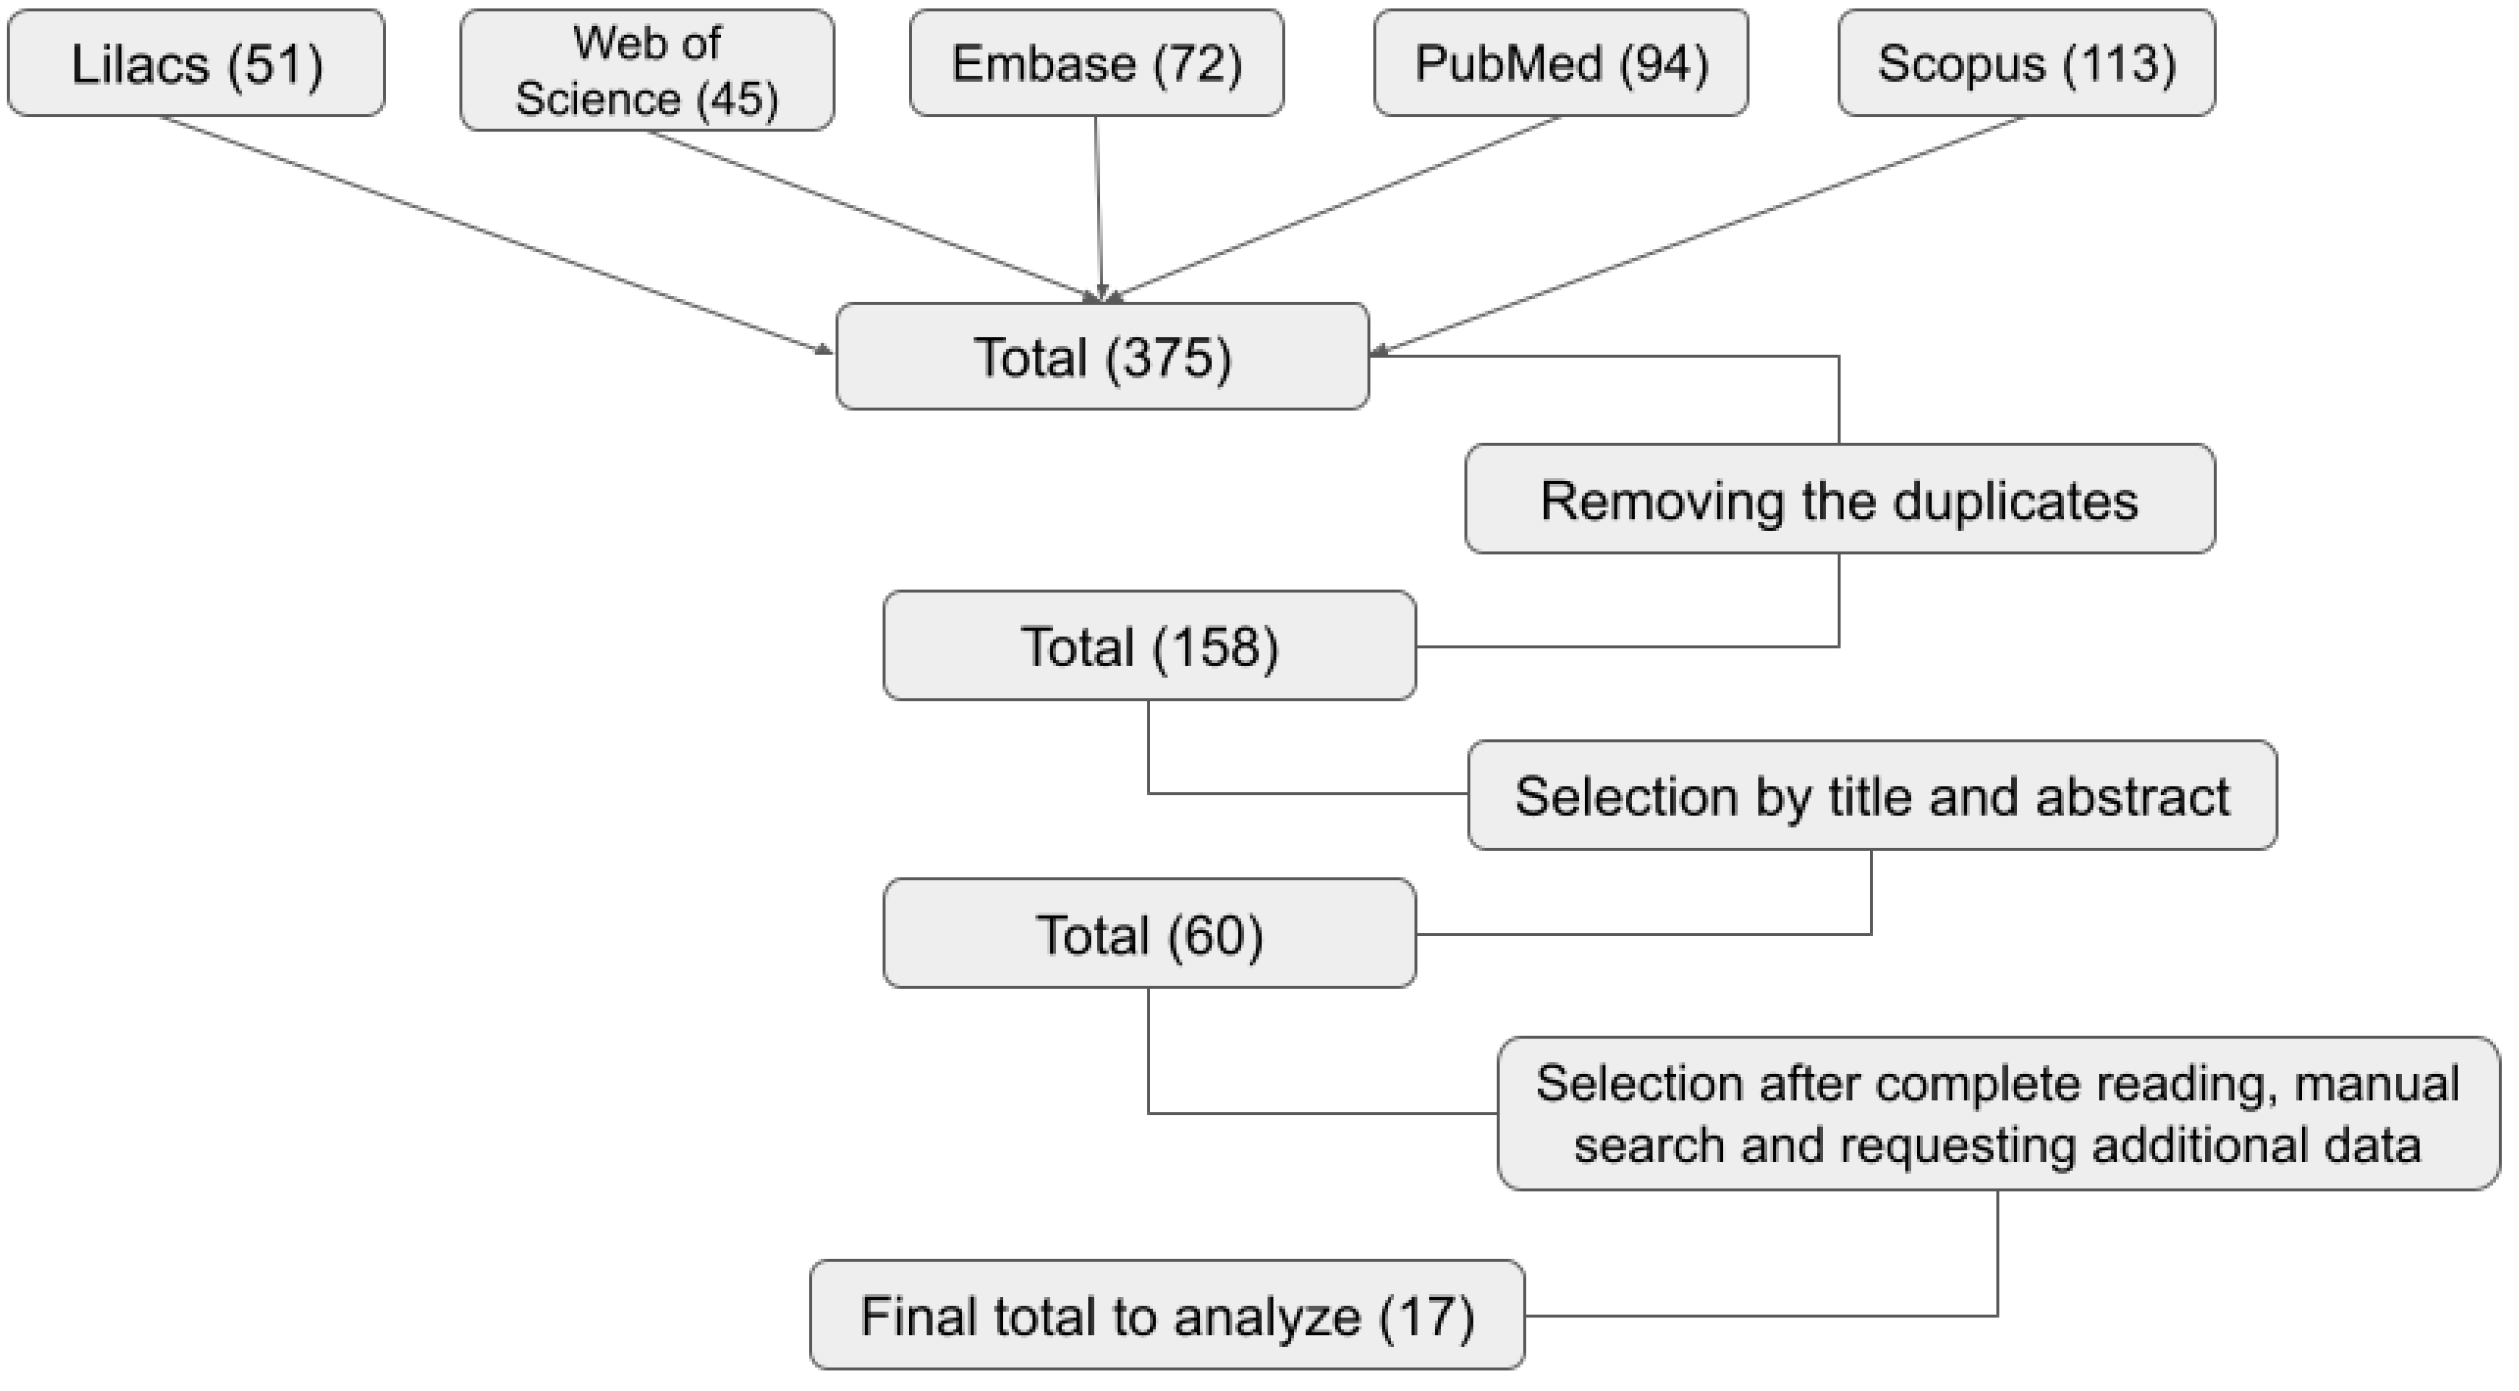
We obtained 375 references between articles and academic works through searches in the databases mentioned in Section 4. Among these, according to the inclusion criteria, seventeen references [21,22,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47] were selected to retrieve data according to the scheme in Figure 1. Files referring to data from the SIREVA II Program of the Pan American Health Organization are available in WHO electronic domains [48,49,50,51,52,53,54,55,56,57,58,59,60,61,62].
Figure 1.
Detailed flowchart for obtaining and selecting eligible articles for this systematic review.
2.1. Assessment of the Methodological Quality of the Articles
Regarding the description and case definition of the population of the studies, only two (11.8%) of seventeen articles were negatively classified. Seven (41.2%) of the seventeen articles described the representativeness of the sample and its sampling in a clear way. All articles described the type of test used and mentioned or referenced the evaluative standard used. However, only five (29.4%) articles described the use of internal quality control. Detailed data can be found in Table 1.
Table 1.
Methodological quality assessment through the modified Newcastle–Ottawa assessment scale [63] adapted from Sugianli et al., 2021 [64] and Mancini et al., 2017 [65].
2.2. Data Extraction
Of the 17 articles selected for this systematic review [21,22,33,34,35,36,37,38,39,40,41,42,43,44,45,46,47], the main information extracted from them is presented in Table 2, divided into parts: a (pre-PCV10 period), b (post-PCV10 period), and c (extended period; those with data from both pre- and post-PCV10 periods).
Table 2.
(a) Main results retrieved from articles with data of the pre-PCV10 period. (b) Main results retrieved from articles with data of the post-PCV10 period. (c) Main results retrieved from article with data of the extended period (covering pre- and post-PCV10 period) with raw data provision.
Considering all the references included in this study, we obtained data on 18,273 isolates; data on 15,437 (84.5%) isolates were provided by SIREVA II (invasive isolates) and data on 2839 (15.5%) isolates were obtained through the included articles. Of 18,273 isolates, 2683 (14.7%) isolates were associated with colonization, 117 (0.6%) isolates with non-invasive diseases, and 39 (0.2%) isolates were associated with invasive diseases, but not presented by SIREVA II. In total, 8991 (49.2%) isolates were from the pre-PCV10 period and 9285 (50.8%) were from the post-PCV10 period.
Invasive isolates included those from sterile sites, such as blood, pleural fluid, and cerebrospinal fluid (CSF). The colonization isolates, obtained through the articles, were mainly collected through sterile swabs in contact with the nasopharynx and oropharynx. Other types of isolates were included in non-invasive pneumococcal diseases, such as ear abscess, cervical abscess, buttock abscess, nasal/eye abscess, bronchial aspirate, corneal aspirate, sinus aspirate, pulmonary aspirate, tracheal aspirate, sputum, bronchoalveolar lavage, auricular secretion, bronchial secretion, tear duct secretion, conjunctival secretion, ocular secretion, wound secretion, skin secretion, pulmonary secretion, postauricular secretion, tracheal secretion, rectal swab, corneal ulcer, and urine.
Antimicrobial resistance data were compiled and organized into tables separated by pre- and post-PCV10 introduction periods (Table 3 and Table 4).
Table 3.
Data related to antimicrobial resistance evaluated in the pre-PCV10 period divided into colonizing, non-invasive, and invasive isolates.
Table 4.
Data related to antimicrobial resistance evaluated in the post-PCV10 introduction period divided into colonizing, non-invasive, and invasive isolates.
Higher frequencies of resistance to sulfamethoxazole-trimethoprim were observed in invasive isolates in the pre-PCV10 period (60.1%; 4815/8016). No case of non-susceptibility (intermediate + resistant) in the pre-PCV10 period was observed for vancomycin, linezolid, trovafloxacin, telithromycin, and quinupristin-dalfopristin, as well as resistance to amoxicillin. In the post-PCV10 introduction period, no resistance was observed to vancomycin, linezolid, telithromycin, and quinupristin-dalfopristin.
Data on susceptibility to penicillin and ceftriaxone were separated into meningitis and non-meningitis and by period, respectively, in Table 5(a,b) and Table 6(a,b).
Table 5.
(a) Data related to penicillin resistance in the pre-PCV10 period divided into meningitis, non-meningitis, and general parameters. (b) Data related to penicillin resistance in the post-PCV10 period divided into meningitis, non-meningitis, and general parameters.
Table 6.
(a) Data related to ceftriaxone resistance in the pre-PCV10 period divided into meningitis, non-meningitis, and general parameters. (b) Data related to ceftriaxone resistance in the post-PCV10 introduction period divided into meningitis, non-meningitis, and general parameters.
For ceftriaxone, we observed a higher proportion of resistance to general in the post-PCV10 introduction period (6.5%, 25/384), similar to penicillin, which showed a higher proportion (44.6%; 499/1118).
Regarding macrolide resistance, a greater volume of data were obtained for erythromycin. There is a high susceptibility for colonization isolates in the pre-PCV10 period (95.2%; 719/755), with a decline in susceptibility in the post-PCV10 period (82%; 596/727). These findings were similar to invasive isolates, which in the pre-PCV10 period were 94.5% susceptible (6795/7186) and 81.1% (6397/7884) in the post-PCV10 period.
Finally, a small number of isolates was tested against fluoroquinolones and, as a result, there are data on ofloxacin and trovafloxacin susceptibility only for the pre-PCV10 period. All ninety-two (100%) carriage isolates tested against ofloxacin and the two (100%) carriage isolates tested against trovafloxacin were susceptible. For invasive (n = 1) and non-invasive (n = 2) disease isolates, the susceptibility against trovafloxacin was also 100%. Levofloxacin had a higher number of susceptible isolates, with a proportion of 98.8% (557/564) in the pre-PCV10 period and 100% (565/565) in the post-PCV10 period for colonization isolates. All the 20 invasive isolates from the pre-PCV10 period were susceptible to levofloxacin. All non-invasive disease isolates from the pre-PCV10 (48/48) and post-PCV10 (22/22) periods were also susceptible to levofloxacin.
2.3. Statistical Analysis
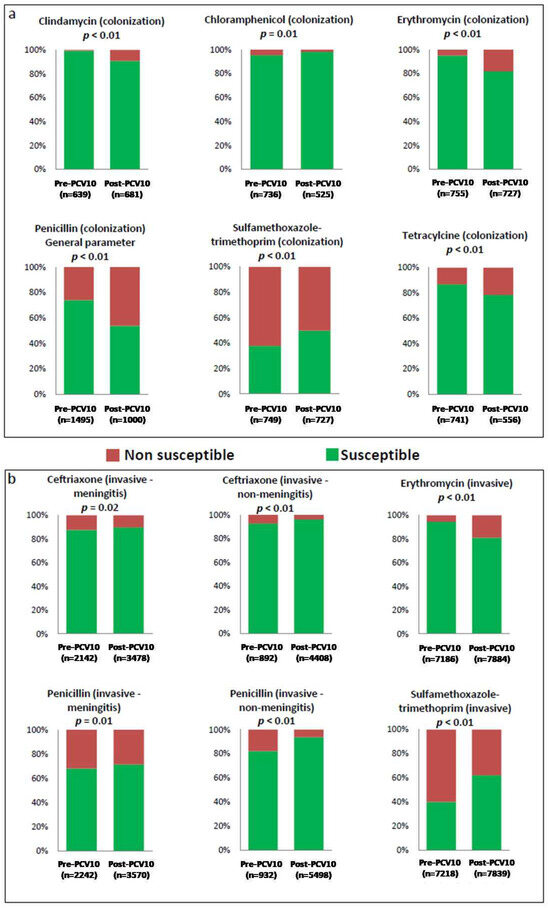
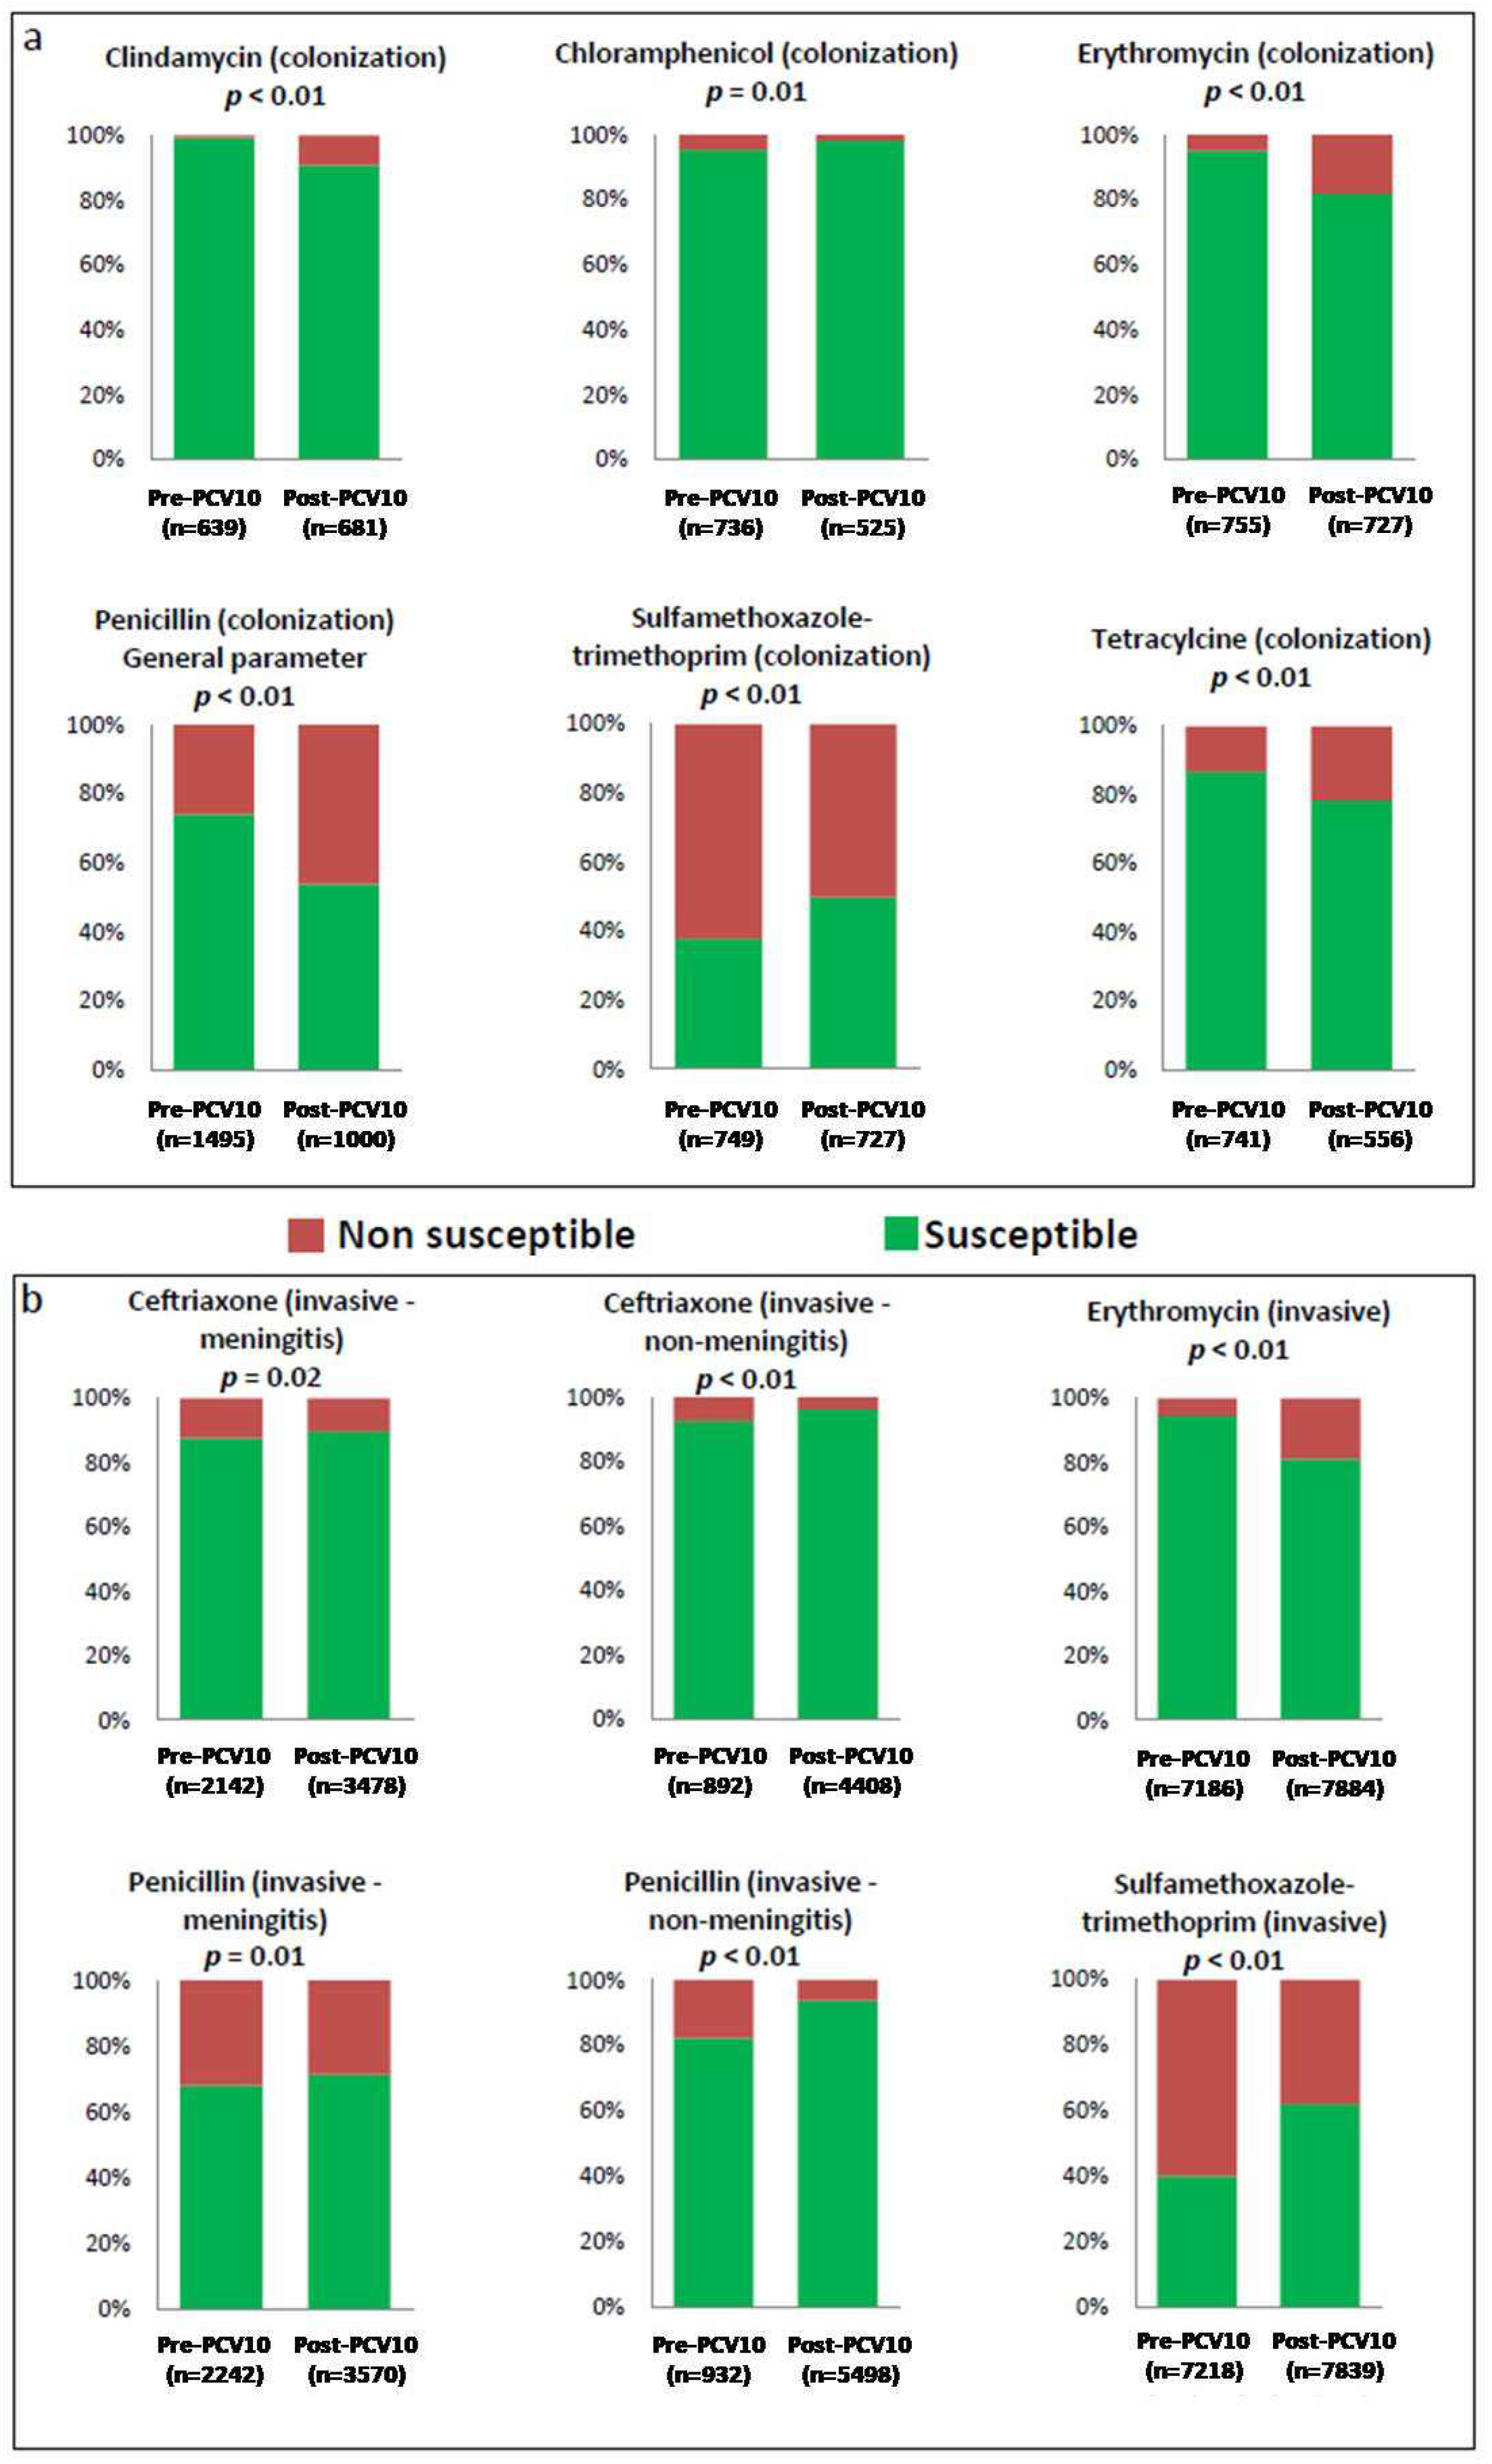
The proportion of erythromycin non-susceptible isolates was higher among carriage (p < 0.01) and invasive (p < 0.01) isolates of the post-PCV10 period. The proportion of sulfamethoxazole-trimethoprim susceptibility (p < 0.01) was higher among isolates of the post-PCV10 period, regardless the isolation source. Although a limited number of isolates has been tested against meropenem, susceptibility to this drug was higher among non-invasive isolates (p < 0.01) of the post-PCV10 period. Among carriage isolates, the frequencies of susceptibility to chloramphenicol (p = 0.01), as well as non-susceptibility to clindamycin (p < 0.01) and tetracycline (p < 0.01), were higher after PCV10 introduction. Among invasive isolates (meningitis and non-meningitis), the proportion of susceptibility to penicillin (p ≤ 0.01) and ceftriaxone (p ≤ 0.02) was higher after PCV10 introduction. On the other hand, the frequency of penicillin non-susceptible pneumococci was higher among carriage isolates (p < 0.01) in the general parameter in the post-PCV10 period. Figure 2 shows the main results of proportion tests when statistically significant differences in the antimicrobial susceptibility profile were detected between isolates of the pre- and post-PCV10 periods.
Figure 2.
The proportion of isolates susceptible and non-susceptible to antimicrobial agents according to isolation source ((a). carriage isolates; (b). invasive isolates) before and after the introduction of the 10-valent pneumococcal conjugate vaccine (PCV10) for universal use in Brazil (p-value was calculated using a two-proportion Z-test to compare independent samplings).
3. Discussion
Based on the 17 articles selected through this systematic literature review, a high number of articles (88.2%; 15/17) were positively classified within the tool used (modified Newcastle–Ottawa assessment scale) [63,64,65], offering greater reliability in the use of the data obtained. Notably, a considerably high number of invasive isolates originated from SIREVA II (84.4%, 15,437/18,276), considered an important epidemiological surveillance tool for S. pneumoniae and other microorganisms in Latin America.
The susceptibility to sulfamethoxazole-trimethoprim (SXT) was higher after PCV10 introduction for routine use in Brazil (p = 0.01). In the pre-PCV10 period among invasive isolates, the proportion of SXT susceptibility and non-susceptibility was 40.3% (2907/7218) and 59.7% (4311/7218), respectively. In the post-PCV10 introduction period, there was a drop in the number of non-susceptible isolates (37.7%; 2957/7839) compared to the susceptible ones (62.3%; 4882/7839). This comparison is interesting because it presents a change in the general panorama of antimicrobial resistance of this drug, tending to a drop in resistance levels. However, it is noteworthy that this phenomenon is not uniformly observed in other countries; for example, a recent study carried out in Malawi (southeast Africa) with colonization and invasive isolates verified a high frequency of resistance to SXT (96%; 137/143), with similar resistance profiles worldwide [66].
For penicillin, there was a statistically significant difference in the percentage of non-susceptibility between the pre- and post-PCV10 introduction periods among invasive isolates, with lower frequencies for both meningitis (31.9% to 28.7%; p = 0.01) and non-meningitis (17.7% to 6.3%; p < 0.01) after PCV10 use. This finding is very important since in Latin America most countries usually report a prevalence of penicillin resistance among meningitis isolates over 30% [62]. On the other hand, regarding the general parameter, there was an increase in non-susceptibility between the same periods from 25.9% (387/1495) to 44.1% (461/1000) for colonization isolates (p < 0.01), respectively. This may be explained mainly by the impact of childhood vaccination with PCV10 in Brazil since before PCV10 introduction, resistance to beta-lactams was mostly associated with serotypes included in the vaccine formulation, especially 6B, 14, 19F, and 23F [38,40,67]. After PCV10 introduction, these serotypes were nearly eliminated from both colonization and diseases [21,22,67].
Due to the serotype replacement phenomenon, some of the main serotypes circulating in Brazil are currently 19A in invasive diseases with high resistance to different classes of antimicrobial agents and 6C in colonization isolates [21,36,40,44]. In this context, a replacement by PCV13, PCV15, PCV20, and even Pneumosil®, which also protects against 10 vaccine serotypes, would be appropriate to replace PCV10 in the Brazilian National Immunization Program [6,9,10,11,19]. However, this phenomenon may continue due to the varied range of capsular serotypes and their distribution among populations.
For ceftriaxone, the general parameter shows a higher frequency of non-susceptible isolates (4.6%; 25/542) in isolates associated with colonization in the post-PCV10 introduction period. Although not statistically significant (p = 0.43), this is of paramount importance since third-generation cephalosporins are frequently used to treat pneumococcal meningitis [26], and isolates with this resistance profile circulating within a population represent a high risk of transmission and development of severe diseases. In turn, susceptibility to ceftriaxone was significantly higher (p ≤ 0.02) among invasive isolates recovered in the post-PCV10 period.
Frequencies of susceptibility to macrolides, namely erythromycin and clarithromycin, exceeded 70% across all periods evaluated. A similar profile between invasive and colonization isolates was observed, with an important decline in susceptibility in the post-PCV10 period. Resistance in the pre-PCV10 period was around 5% for both colonization and invasive isolates. However, the proportion of macrolide-resistant isolates almost reached 20% in the post-PCV10 period. Macrolide resistance has been increasing worldwide. A nationwide surveillance in the USA between 2018 and 2019, with isolates recovered from blood and respiratory specimens from adults, revealed a high burden of macrolide resistance among S. pneumoniae, reaching almost 40% [68].
Levofloxacin is the fluoroquinolone with the greatest amount of data available for analysis, and the authors observed a high proportion of susceptibility among colonization isolates in the pre-PCV10 (98.8%; 557/564) and the post-PCV10 (100%; 565/565) periods. A similar scenario was observed for invasive isolates, in which all isolates (24 isolates from pre-PCV10 and 50 isolates from post-PCV10 periods) were susceptible to fluoroquinolones.
Despite the increasing and worrying resistance to beta-lactams and macrolides, all isolates were susceptible to vancomycin, linezolid, telithromycin, and quinupristin-dalfopristin in both the pre- and post-PCV10 introduction periods.
The main limitation of this work was the high variation of data presentation in the articles included in this review, making it difficult to group them. Also, 22 articles with important data were not made available in time by the authors, despite attempts to contact them. Still, we retrieved data on an extensive collection of isolates recovered from various clinical sources, mainly associated with IPD, and from different geographical regions of Brazil, providing a comprehensive scenario of antimicrobial resistance in pneumococci before and after PCV introduction for routine use in Brazil.
4. Materials and Methods
4.1. Search Strategy
This systematic review was structured between May 2022 and July 2023 with the search date on 23 May 2023. The following databases were consulted: Lilacs (Latin American & Caribbean Health Sciences Literature), Embase, Pubmed, Scopus, and Web of Science. In addition to these, a manual search was carried out in the bibliographic references of the selected articles and data extraction from the documents was produced by the System of Surveillance Networks of Responsible Agents for Bacterial Pneumonia and Meningitis (SIREVA II; Electronic page: https://www3.paho.org/hq/index.php?option=com_docman&view=list&slug=sireva-ii-8059&Itemid=270&lang=pt#gsc.tab=0; accessed on 23 May 2023).
The files referring to the search strategies according to the base can be found in the Supplementary Material as Table S1 and the manual search as Table S2.
This review was based on the question: “How is the resistance profile to antimicrobial agents of Streptococcus pneumoniae isolates before and after the introduction of pneumococcal conjugate vaccines in Brazil?”. It is noteworthy that this research was submitted to the Prospero platform [PROSPERO acknowledgment of receipt (364743)].
4.2. Article Selection and Data Extraction
All articles found were initially evaluated based on titles and abstracts. After this step, some articles were selected for full reading based on the inclusion and exclusion criteria listed in Table 7.
Table 7.
Criteria used for article selection.
Two authors performed these steps and a third author was consulted in case of doubt. Then, data were extracted using the Microsoft Excel® program.
4.3. Quality Assessment
Individual quality control of each academic work was evaluated according to the Newcastle–Ottawa Quality Tool Assessment Scale with modifications according to models by Sugianli et al., 2021 and Mancini et al., 2017 for cross-sectional studies and according to data demand [63,64,65].
4.4. Data Compilation
The data obtained were compiled and analyzed using Excel®, allowing the division of data according to the vaccination period: pre- or post-PCV introduction in the Brazilian immunization program.
In the case of penicillin and ceftriaxone (beta-lactams), from 2007 onwards, the evaluation parameters were divided into two groups: meningitis and non-meningitis [69]. Data from articles with these definitions were added to their respective classifications (meningitis and non-meningitis). Articles that did not use the parameters listed above for beta-lactams were assigned to the general parameter column for better organization and analysis of the data. Furthermore, when the data were provided by the authors (raw data), in the case of penicillin specifically, originating from sources of colonization (non-invasive), the parameters of oral penicillin were used and the data were added in the general column; when invasive, meningitis and non-meningitis parameters were used. In the case of ceftriaxone, meningitis criteria were applied for invasive isolates and non-meningitis for colonization isolates.
Articles presenting data from a long time covering both periods (pre- and post-PCV10 introduction) had their data organized separately.
We retrieved data for the following classes of antimicrobial agents: amphenicols (chloramphenicol), macrolides (erythromycin, clarithromycin), sulfonamides and diaminopyrimidines (sulfamethoxazole-trimethoprim), glycopeptides (vancomycin), lincosamides (clindamycin), tetracyclines (tetracycline), ansamycins (rifampicin), fluoroquinolones (levofloxacin, ofloxacin, gemifloxacin, trovafloxacin), oxazolidinones (linezolid), ketolides (telithromycin), streptogramins (quinupristin-dalfopristin), and beta-lactams (penicillin, amoxicillin, meropenem, cefotaxime, cefuroxime, oxacillin).
The data obtained were divided into a table with three different parts, namely, part a (pre-PCV10 period), referring to academic works prior to 2010 [34,35,36,37,39,40,43,47]; b (post-PCV10 period), composed of articles with data after the same year [21,22,38,41,42,44,45,46]; and c (extended period), formed by works that contain data from both periods [33].
It is also noteworthy that among the works that required data supplementation, we received only the raw data from the article by Pinto et al. 2019 [33] on time for this study. In this context, the data were separated into three distinct groups according to the scope of this systematic literature review.
4.5. Statistical Analysis
We used a two-proportion Z-test to compare independent samplings, at a confidence level of 95%, and verify if the proportion of pneumococci non-susceptible to antimicrobial agents has significantly changed in the post-PCV10 period.
4.6. Ethical Aspects
All included studies were approved by their respective Ethics Committees. Other data were retrieved from a public database.
5. Conclusions
There is evidence that the proportion of isolates that are susceptible to chloramphenicol and sulfamethoxazole-trimethoprim is higher after PCV10 implementation for routine use in Brazil. More importantly, the same scenario was observed for penicillin and ceftriaxone among isolates associated with IPD. However, it is important to highlight the higher frequency of penicillin non-susceptible pneumococci associated with colonization in the post-PCV10 introduction period due to the emphasis on its use in the treatment of pneumococcal diseases. The emergence of macrolide-resistant isolates, associated with both colonization and diseases, is also a concern. Similarly, resistance to clindamycin and tetracycline is significantly higher among carriage isolates of the post-PCV10 period. On the other hand, susceptibility to other antimicrobial agents, such as ansamycins, fluoroquinolones, glycopeptides, and oxazolidinones, remains high, making them available as alternatives for use as monotherapy or in combined therapy.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/antibiotics13010066/s1, File S1: Article search strategies according to the database; File S2: Articles included after manual search.
Author Contributions
F.P.G.N., H.C.C.P., P.A.K.-P. and A.S.C. contributed to the overall design of the study. F.P.G.N., H.C.C.P., P.A.K.-P., A.S.C., A.B.d.S. and Í.M.D. performed formal analyses. F.P.G.N. and P.A.K.-P. wrote the original draft of the manuscript. F.P.G.N., H.C.C.P., P.A.K.-P., A.S.C. and A.B.d.S. reviewed and edited the manuscript. All authors have read and agreed to the published version of the manuscript.
Funding
This work was funded in part by Conselho Nacional de Desenvolvimento Científico e Tecnológico (CNPq), Coordenação de Aperfeiçoamento de Pessoal de Nível Superior (CAPES)—Finance Code 001, Fundação Carlos Chagas Filho de Amparo à Pesquisa do Estado do Rio de Janeiro (FAPERJ; grant #E-26/211.554/2019—Programa Rede de Pesquisa em Saúde, grant #E-26/010.002141/2019 and grant #E-26/200.855/2021), Pró-Reitoria de Pesquisa, Pós-Graduação e Inovação da Universidade Federal Fluminense (PROPPi/UFF), and Prefeitura de Niterói (PDPA Project #4387).
Institutional Review Board Statement
All included studies were approved by their respective Ethics Committees. Other data were retrieved from a public database.
Acknowledgments
We thank all the funding agencies that helped conduct this work and the authors who made their data available for analysis.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Weiser, J.N.; Ferreira, D.M.; Paton, J.C. Streptococcus pneumoniae: Transmission, colonization and invasion. Nat. Rev. Microbiol. 2018, 16, 355–367. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kadioglu, A.; Weiser, J.N.; Paton, J.C.; Andrew, P.W. The role of Streptococcus pneumoniae virulence factors in host respiratory colonization and disease. Nat. Rev. Microbiol. 2008, 6, 288–301. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Drijkoningen, J.J.C.; Rohde, G.G.U. Pneumococcal infection in adults: Burden of disease. Clin. Microbiol. Infect. 2014, 20, 45–51. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ludwig, E.; Bonanni, P.; Rohde, G.; Sayiner, A.; Torres, A. The remaining challenges of pneumococcal disease in adults. Eur. Respir. Rev. 2012, 21, 57–65. [Google Scholar] [CrossRef] [Scilit]
- Briles, D.E.; Paton, J.C.; Mukerji, R.; Swiatlo, E.; Crain, M.J. Pneumococcal vaccines. Microbiol. Spectr. 2019, 7. [Google Scholar] [CrossRef] [Scilit]
- Rappuoli, R.; De Gregorio, E.; Costantino, P. On the mechanisms of conjugate vaccines. Proc. Natl. Acad. Sci. USA 2019, 116, 14–16. [Google Scholar] [CrossRef] [Scilit]
- Pneumococcal 7-Valent Conjugate Vaccine (Diphtheria CRM197 Protein) Prevnar®. European Medicines Agency: London, UK. Available online: https://www.fda.gov/vaccines-blood-biologics/vaccines/prevnar (accessed on 17 July 2023).
- Synflorix: Pneumococcal Polysaccharide Conjugate Vaccine (Adsorbed). European Medicines Agency: London, UK. Available online: http://www.ema.europa.eu/docs/en_GB/document_library/EPAR_-_Product_Information/human/000973/WC500054346.Pdf (accessed on 17 July 2023).
- Approved Products: Prevnar 13: Pneumococcal 13-Valent Conjugate Vaccine (Diphtheria CRM 197 Protein). Food and Drug Administration: Washington, DC, USA. Available online: https://www.fda.gov/downloads/BiologicsBloodVaccines/Vaccines/ApprovedProducts/UCM574852.pdf (accessed on 17 July 2023).
- Food and Drug Administration. Summary Basis for Regulatory Action—PREVNAR20. US Department of Health and Human Services, Food and Drug Administration: Silver Spring, MD, USA. Available online: https://www.fda.gov/media/150388/download (accessed on 17 July 2023).
- Food and Drug Administration. Summary Basis for Regulatory Action—VAXNEUVANCE. US Department of Health and Human Services, Food and Drug Administration: Silver Spring, MD, USA. Available online: https://www.fda.gov/media/151201/download (accessed on 17 July 2023).
- Huang, L.; Wasserman, M.; Grant, L.; Farkouh, R.; Snow, V.; Arguedas, A.; Chilson, E.; Sato, R.; Perdrizet, J. Burden of pneumococcal disease due to serotypes covered by the 13-valent and new higher-valent pneumococcal conjugate vaccines in the United States. Vaccine 2022, 40, 4700–4708. [Google Scholar] [CrossRef] [Scilit]
- Brasil Departamento de Vigilância Epidemiológica, Secretaria de Vigilância em Saúde, Ministério da Saúde. Informe técnico da vacina pneumocócica 10-valente (conjugada). Brasília: Ministério da Saúde (Série A. Normas e Manuais Técnicos). Available online: http://epidemiologia.alfenas.mg.gov.br/download/informe_t%C3%A9cnico_pneumo_.pdf (accessed on 17 July 2023).
- Brasil Ministério da Saúde. Secretaria de Ciência, Tecnologia e Insumos Estratégicos. Portaria nº 14, de 1º de março de 2019. Torna pública a decisão de incorporar a vacina pneumocócica conjugada 13-valente contra doenças pneumocócicas em pacientes de risco, no âmbito do Sistema Único de Saúde—SUS. Diário Oficial da União, Brasília, DF, 6 de março de 2019. p. 79. Available online: https://bvsms.saude.gov.br/bvs/saudelegis/sctie/2019/prt0014_06_03_2019.html (accessed on 29 October 2023).
- Brasil Ministério da Saúde. Programa Nacional de Imunizações: 30 anos. Brasília: Ministério da Saúde; 2003. 212p. Série C. Projetos e Programas e Relatórios. Available online: https://bvsms.saude.gov.br/bvs/publicacoes/livro_30_anos_pni.pdf (accessed on 1 November 2023).
- Brasil Ministério da Saúde, Secretaria de Vigilância em Saúde, Departamento de Vigilância Epidemiológica. Programa Nacional de Imunizações (PNI): 40 anos. Brasília: Ministério da Saúde; 2013; 236p. Available online: https://bvsms.saude.gov.br/bvs/publicacoes/programa_nacional_imunizacoes_pni40.pdf (accessed on 1 November 2023).
- Sociedade Brasileira de Imunizações—SBIM. Vacinas pneumocócicas conjugadas. 2023. Available online: https://familia.sbim.org.br/vacinas/vacinas-disponiveis/vacinas-pneumococicas-conjugadas (accessed on 29 October 2023).
- Jefferies, J.M.; Macdonald, E.; Faust, S.N.; Clarke, S.C. 13-valent pneumococcal conjugate vaccine (PCV13). Hum. Vaccines 2011, 7, 1012–1018. [Google Scholar] [CrossRef] [Scilit]
- Jarovsky, D.; Berezin, E.N. Impact of PCV10 on pediatric pneumococcal disease burden in Brazil: Time for new recommendations? J. Pediatr. 2023, 99, S46–S56. [Google Scholar] [CrossRef] [Scilit]
- Brasil Ministério da Saúde. DATASUS. Brasília: Ministério da Saúde; 2023. Available online: http://tabnet.datasus.gov.br/cgi/dhdat.exe?bd_pni/cpnibr.def/ (accessed on 26 December 2023).
- Neves, F.P.G.; Cardoso, N.T.; Snyder, R.E.; Marlow, M.A.; Cardoso, C.A.A.; Teixeira, L.M.; Riley, L.W. Pneumococcal carriage among children after four years of routine 10-valent pneumococcal conjugate vaccine use in Brazil: The emergence of multidrug resistant serotype 6C. Vaccine 2017, 35, 2794–2800. [Google Scholar] [CrossRef] [Scilit]
- Fortuna, L.B.; Miranda, F.M.; Antunes, I.M.; Silva, A.B.; Cabral, A.S.; Dolores, I.M.; Cardoso-Marques, N.T.; Teixeira, L.M.; Neves, F.P. Prevalence, capsular types, antimicrobial resistance and risk factors associated with pneumococcal carriage among children after long-term 10-valent pneumococcal conjugate vaccine use in Brazil. Vaccine 2023, 41, 3111–3118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kupek, E.; Vieira, I.L.V. O impacto da vacina pneumocócica PCV10 na redução da mortalidade por pneumonia em crianças menores de um ano em Santa Catarina, Brasil. Cad. Saúde Pública 2016, 32, e00131414. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Andrade, A.L.; Afonso, E.T.; Minamisava, R.; Bierrenbach, A.L.; Cristo, E.B.; Morais-Neto, O.L.; Policena, G.M.; Domingues, C.M.A.S.; Toscano, C.M. Direct and indirect impact of 10-valent pneumococcal conjugate vaccine introduction on pneumonia hospitalizations and economic burden in all age-groups in Brazil: A time-series analysis. PLoS ONE 2017, 12, e0184204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brasil Ministério da Saúde/SVS—Sistema de Informação de Agravos de Notificação—Sinan Net. Available online: http://tabnet.datasus.gov.br/cgi/deftohtm.exe?sinannet/cnv/meninbr.def (accessed on 13 October 2023).
- Von Specht, M.; García Gabarrot, G.; Mollerach, M.; Bonofiglio, L.; Gagetti, P.; Kaufman, S.; Vigliarolo, L.; Toresani, I.; Lopardo, H.A. Resistance to β-lactams in Streptococcus pneumoniae. Rev. Argent. Microbiol. 2021, 53, 266–271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cherazard, R.; Epstein, M.; Doan, T.L.; Salim, T.; Bharti, S.; Smith, M.A. Antimicrobial resistant Streptococcus pneumoniae: Prevalence, mechanisms, and clinical implications. Am. J. Ther. 2017, 24, e361–e369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Domínguez-Alegría, A.R.; Pintado, V.; Barbolla, I. Treatment and prevention of invasive pneumococcal disease. Rev. Clin. Esp. (Engl. Ed.) 2018, 218, 244–252. [Google Scholar] [CrossRef]
- Gaddey, H.L.; Wright, M.T.; Nelson, T.N. Otitis media: Rapid evidence review. Am. Fam. Physician 2019, 100, 350–356. Available online: https://www.aafp.org/pubs/afp/issues/2019/0915/p350.pdf (accessed on 17 July 2023).
- Modi, A.R.; Kovacs, C.S. Community-acquired pneumonia: Strategies for triage and treatment. Cleve. Clin. J. Med. 2020, 87, 145–151. [Google Scholar] [CrossRef] [Scilit]
- World Health Organization (WHO). WHO Publishes List of Bacteria for Which New Antibiotics Are Urgently Needed. 2017. Available online: https://www.who.int/news-room/detail/27-02-2017-who-publishes-list-of-bacteria-for-which-new-antibiotics-are-urgently-needed (accessed on 17 July 2023).
- Centers for Disease Control and Prevention (CDC). Antimicrobial Resistance: 2019 AR Threats Report. 2019. Available online: https://www.cdc.gov/drugresistance/biggest-threats.html (accessed on 29 October 2023).
- Pinto, T.C.A.; Neves, F.P.G.; Souza, A.R.V.; Oliveira, L.M.A.; Costa, N.S.; Castro, L.F.S.; Mendonça-Souza, C.R.d.V.; Peralta, J.M.; Teixeira, L.M. Evolution of Penicillin Non-susceptibility Among Streptococcus pneumoniae Isolates Recovered from Asymptomatic Carriage and Invasive Disease over 25 years in Brazil, 1990–2014. Front. Microbiol. 2019, 10, 486. [Google Scholar] [CrossRef] [Scilit]
- Velasquez, P.A.; Parussolo, L.; Cardoso, C.L.; Tognim, M.C.B.; Garcia, L.B. High prevalence of children colonized with penicillin-resistant Streptococcus pneumoniae in public day-care centers. J. Pediatr. (Rio J.) 2009, 85, 516–522. [Google Scholar] [CrossRef] [Scilit]
- Pereira, M.; Pereira, M.R.; Cantarelli, V.; Costa, S.S. Prevalence of bacteria in children with otitis media with effusion. J. Pediatr. (Rio J.) 2004, 80, 41–48. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cardozo, D.M.; Nascimento-Carvalho, C.M.; Brandão, M.A.; Azevedo, G.M.S.; De Souza, F.R.; Silva, N.M.S.; Brandão, A.P.; Andrade, A.L.; Brandileone, M.C.C. Antimicrobial resistance and serotypes of nasopharyngeal strains of Streptococcus pneumoniae in Brazilian adolescents. Microb. Drug Resist. 2006, 12, 29–32. [Google Scholar] [CrossRef] [Scilit]
- Franco, C.M.; Andrade, A.L.S.; Andrade, J.G.; e Silva, S.A.; Oliveira, C.R.M.; Pimenta, F.C.; Lamaro-Cardoso, J.; Brandão, A.P.; Almeida, S.C.G.; Calix, J.J.; et al. Survey of nonsusceptible nasopharyngeal Streptococcus pneumoniae isolates in children attending day-care centers in Brazil. Pediatr. Infect. Dis. J. 2010, 29, 77. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neves, F.P.; Cardoso, N.T.; Cardoso, C.A.; Teixeira, L.M.; Riley, L.W. Direct effect of the 13-valent pneumococcal conjugate vaccine use on pneumococcal colonization among children in Brazil. Vaccine 2019, 37, 5265–5269. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reis, J.N.; Palma, T.; Ribeiro, G.S.; Pinheiro, R.M.; Ribeiro, C.T.; Cordeiro, S.M.; Da Silva Filho, H.P.; Moschioni, M.; Thompson, T.A.; Sprat, B.; et al. Transmission of Streptococcus pneumoniae in an urban slum community. J. Infect. 2008, 57, 204–213. [Google Scholar] [CrossRef] [Scilit]
- Neves, F.P.G.; Pinto, T.C.A.; Corrêa, M.A.; Barreto, R.A.; Moreira, L.S.G.; Rodrigues, H.G.; Cardoso, C.A.; Barros, R.R.; Teixeira, L.M. Nasopharyngeal carriage, serotype distribution and antimicrobial resistance of Streptococcus pneumoniae among children from Brazil before the introduction of the 10-valent conjugate vaccine. BMC Infect. Dis. 2013, 13, 318. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Laranjeira, B.J. Resistência antimicrobiana, genotipagem capsular e detecção de genes de resistência de Streptococcus pneumoniae isolados de crianças não vacinadas usuárias de creches em Fortaleza. Ph.D. Thesis, Federal University of Ceara, Fortaleza, Brazil, 2014. Available online: https://repositorio.ufc.br/handle/riufc/15459 (accessed on 18 July 2023).
- Da Silva, A.B.; Cardoso-Marques, N.T.; Dolores, I.M.; Teixeira, L.M.; Neves, F.P.G. Carriage prevalence, serotype distribution, antimicrobial resistance, pspA typing and pilus islets of Streptococcus pneumoniae isolated from adults living in a Brazilian urban slum. Vaccine 2023, 41, 1431–1437. [Google Scholar] [CrossRef] [Scilit]
- Fonseca, P.B.B.; Braga, J.A.P.; Machado, A.M.D.O.; Brandileone, M.C.D.C.; Farhat, C.K. Colonização nasofaríngea pelo Streptococcus pneumoniae em crianças com doença falciforme usando penicilina profilática. J. Pediatr. (Rio J.) 2005, 81, 149–154. [Google Scholar] [CrossRef] [Scilit]
- Brandileone, M.C.D.C.; Zanella, R.C.; Almeida, S.C.; Cassiolato, A.P.; De Lemos, A.P.S.; Salgado, M.M.; Higa, F.T.; Minamisava, R.; Andrade, A.L. Long-term effect of 10-valent pneumococcal conjugate vaccine on nasopharyngeal carriage of Streptococcus pneumoniae in children in Brazil. Vaccine 2019, 37, 5357–5363. [Google Scholar] [CrossRef] [Scilit]
- Zanella, R.C.; Brandileone, M.C.D.C.; Almeida, S.C.G.; De Lemos, A.P.S.; Sacchi, C.T.; Gonçalves, C.R.; Gonçalves, M.G.; Fukasawa, L.O.; Saraiva, M.D.; Rangel, L.F.; et al. Nasopharyngeal carriage of Streptococcus pneumoniae, Haemophilus influenzae, and Staphylococcus aureus in a Brazilian elderly cohort. PLoS ONE 2019, 14, e0221525. [Google Scholar] [CrossRef] [Scilit]
- Rezende, R.P.V.D.; Cardoso-Marques, N.T.; Rodrigues, L.A.S.; Almeida, J.P.C.L.D.; Pillegi, G.S.; Teixeira, L.M.; Klumb, E.M.; Neves, F.P.G. Carriage prevalence, serotype distribution, and antimicrobial susceptibility among pneumococcal isolates recovered from adults with systemic lupus erythematosus. Lupus 2021, 30, 1863–1865. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Laval, C.B.; De Andrade, A.L.S.S.; Pimenta, F.C.; De Andrade, J.G.; De Oliveira, R.M.; Silva, S.A.; De Lima, E.C.; Di Fabio, J.L.; Casagrande, S.T.; Brandileone, M.C.C. Serotypes of carriage and invasive isolates of Streptococcus pneumoniae in Brazilian children in the era of pneumococcal vaccines. Clin. Microbiol. Infect. 2006, 12, 50–55. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- World Health Organization [Homepage on the Internet]. OPAS. Available online: https://www3.paho.org/hq/index.php?option=com_docman&view=list&slug=sireva-ii-8059&Itemid=270&lang=pt#gsc.tab=0 (accessed on 18 July 2023).
- Organización Panamericana de la Salud. Informe Regional de SIREVA II: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis en procesos invasores, 2000–2005; OPS: Washington, DC, USA, 2007; Available online: https://www.paho.org/es/node/72322 (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe Regional de SIREVA II, 2006: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis en procesos invasores; OPS: Washington, DC, USA, 2008; Available online: https://www.paho.org/es/documentos/informe-regional-sireva-ii-2006 (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe Regional de SIREVA II, 2007: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis en procesos invasores; OPS: Washington, DC, USA, 2008; Available online: https://www3.paho.org/hq/dmdocuments/2009/SirevaII2007.pdf (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe Regional de SIREVA II, 2008: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis en procesos invasores; OPS: Washington, DC, USA, 2009; Available online: https://www3.paho.org/hq/dmdocuments/2012/Informe-Regional-SIREVAII-2008.pdf (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe Regional de SIREVA II, 2009: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis en procesos invasores; OPS: Washington, DC, USA, 2010; Available online: https://www3.paho.org/hq/dmdocuments/2010/SIREVA%20II%202009.pdf (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe Regional de SIREVA II, 2010: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis en procesos invasores; OPS: Washington, DC, USA, 2011; Available online: https://www3.paho.org/hq/dmdocuments/2011/SIREVA-II-2010.pdf (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe Regional de SIREVA II, 2011: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis en procesos invasores; OPS: Washington, DC, USA, 2012; Available online: https://www3.paho.org/hq/dmdocuments/2012/SIREVA-II-2011-Sp.pdf (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe Regional de SIREVA II, 2012: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis en procesos invasores; OPS: Washington, DC, USA, 2013; Available online: https://www3.paho.org/hq/index.php?option=com_docman&view=download&alias=30766-informe-regional-sireva-ii-2012-766&category_slug=sireva-ii-8059&Itemid=270&lang=pt (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe Regional de SIREVA II, 2013: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis en procesos invasivos bacterianos; OPS: Washington, DC, USA, 2016; Available online: https://iris.paho.org/handle/10665.2/31147 (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe regional de SIREVA II, 2014: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis, em procesos invasivos bacterianos; OPS: Washington, DC, USA, 2017; Available online: https://iris.paho.org/handle/10665.2/33875 (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe regional de SIREVA II, 2015: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis, em procesos invasivos bacterianos; OPS: Washington, DC, USA, 2018; Available online: https://iris.paho.org/bitstream/handle/10665.2/49091/9789275320099_spa.pdf?ua=1 (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe regional de SIREVA II, 2016: Datos por país y por grupos de edad sobre las características de los aislamientos de Streptococcus pneumoniae, Haemophilus influenzae y Neisseria meningitidis, em procesos invasivos bacterianos; OPS: Washington, DC, USA, 2019; Available online: https://iris.paho.org/handle/10665.2/51781 (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe regional de SIREVA II, 2017; OPS: Washington, DC, USA, 2020; Available online: https://iris.paho.org/handle/10665.2/53136 (accessed on 12 November 2023).
- Organización Panamericana de la Salud. Informe regional de SIREVA II, 2018; OPS: Washington, DC, USA, 2021; Available online: https://iris.paho.org/handle/10665.2/54567 (accessed on 12 November 2023).
- Wells, G.A.; Shea, B.; O’Connell, D.; Peterson, J.; Welch, V.; Losos, M.; Tugwell, P. The Newcastle-Ottawa Scale (NOS) for Assessing the Quality of Nonrandomised Studies in Meta-Analyses. 2021. Available online: http://www.ohri.ca/programs/clinical_epidemiology/oxford.asp (accessed on 19 July 2023).
- Sugianli, A.K.; Ginting, F.; Parwati, I.; de Jong, M.D.; van Leth, F.; Schultsz, C. Antimicrobial resistance among uropathogens in the Asia-Pacific region: A systematic review. JAC Antimicrob. Resist. 2021, 3, dlab003. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mancini, E.; Beglinger, C.; Drewe, J.; Zanchi, D.; Lang, U.E.; Borgwardt, S. Green tea effects on cognition, mood and human brain function: A systematic review. Phytomedicine 2017, 34, 26–37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cornick, J.E.; Harris, S.R.; Parry, C.M.; Moore, M.J.; Jassi, C.; Kamng’ona, A.; Kulohoma, B.; Heyderman, R.S.; Bentley, S.D.; Everett, D.B. Genomic identification of a novel co-trimoxazole resistance genotype and its prevalence amongst Streptococcus pneumoniae in Malawi. J. Antimicrob. Chemother. 2014, 69, 368–374. [Google Scholar] [CrossRef] [Scilit]
- Domingues, C.M.; Verani, J.R.; Montenegro Renoiner, E.I.; de Cunto Brandileone, M.C.; Flannery, B.; de Oliveira, L.H.; Santos, J.B.; de Moraes, J.C. Brazilian Pneumococcal Conjugate Vaccine Effectiveness Study Group. Effectiveness of ten-valent pneumococcal conjugate vaccine against invasive pneumococcal disease in Brazil: A matched case-control study. Lancet Respir. Med. 2014, 2, 464–471. [Google Scholar] [CrossRef] [Scilit]
- Gupta, V.; Yu, K.C.; Schranz, J.; Gelone, S.P. A multicenter evaluation of the US prevalence and regional variation in macrolide-resistant S. pneumoniae in ambulatory and hospitalized adult patients in the United States. Open Forum Infect. Dis. 2021, 8, ofab063. [Google Scholar] [CrossRef] [Scilit]
- Clinical and Laboratory Standards Institute. Performance Standards for Antimicrobial Susceptibility Testing (CLSI) M100-S17. Clinical and Laboratory Standards Institute: Wayne, PA, USA, 2007. [Google Scholar]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2024 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).