


Abstract
Blood viscosity is strongly dependent on hematocrit, and the hematocrit–viscosity relationship is an important determinant of blood rheology under physiological and pathological conditions. However, obtaining a full hematocrit–viscosity curve requires multiple measurements over a wide hematocrit range. In this study, a simple method is proposed to reconstruct the full hematocrit–viscosity curve using only three-dataset Krieger–Dougherty (K–D) regression as . Based on suspended blood, RBC-rich blood and RBC-depleted blood are prepared after centrifugation. The hematocrit of each type of blood is measured using a micro-hemocytometer. Simultaneously, the blood viscosity of each type of blood is measured using the coflowing streams method. The proposed method is evaluated sequentially using reference datasets and hematocrit–viscosity datasets of control blood. According to results, the full hematocrit–viscosity curve obtained from three selected datasets is in good agreement with the experimental data and yields a lower root-mean-square error than conventional methods using all datasets. The exponent of the K–D model is strongly influenced by the midpoint dataset, whereas μ0 is mainly affected by the suspending medium (dextran solution). In contrast, GA-induced rigidified RBCs do not significantly affect μ0 within a 0.15% concentration. In conclusion, the proposed method provides a simple, efficient, and reliable approach for estimating the full hematocrit–viscosity curve.
1. Introduction
Blood consists of plasma and cellular components (i.e., red blood cells [RBCs], white blood cells, and platelets) [1]. Blood viscosity is a rheological property that represents the resistance of shearing blood flow, which is defined as the ratio of shear stress to shear rate. Clinically, blood viscosity plays a critical role in determining vascular resistance, microcirculatory blood flow, and tissue oxygen supply [2]. An abnormal increase in blood viscosity can hinder blood flow and is closely related to cardiovascular risk [3,4], thrombosis, ischemia, and diabetes [5,6]. Accordingly, blood viscosity is regarded not only as a basic physical parameter of blood circulation, but also as a promising biomarker for evaluating hemorheological abnormalities and the progression of disease.
Blood viscosity is determined by several factors, including, hematocrit [7,8,9,10,11,12,13,14,15], plasma composition [4,16,17,18,19,20,21], and RBC rheological properties (i.e., aggregation [22,23,24,25,26,27,28,29,30] and deformability [31,32,33,34,35,36]). Blood viscosity is governed by the shear rate of blood flow (i.e., non-Newtonian fluid). Among the factors influencing blood viscosity, hematocrit is the most important factor affecting blood viscosity. In other words, when blood hematocrit increases, the RBCs become more crowded, which makes blood flow more difficult. Consequently, it contributes to increasing blood viscosity [1,2,10,15,37,38,39,40,41].
When blood viscosity is described solely as a function of hematocrit, the corresponding regression model has been progressively refined from a simple linear approximation to a nonlinear asymptotic form. The earliest expression is the Einstein-type relation (i.e., ). Herein, μ, μ0, and ϕ denote blood viscosity, plasma viscosity, and hematocrit, respectively. However, this equation is valid only at very low hematocrit levels (i.e., ϕ < 0.1) and does not adequately describe whole blood over the physiological hematocrit range. This limitation is later addressed by the finite concentration model [42] and more fully resolved by the Krieger–Dougherty (K-D) model [43,44], . Herein, a maximum packing factor () is introduced to represent the steep rise in blood viscosity as hematocrit approaches its upper limit. The exponent (α) represents both contributions of RBCs to blood viscosity and maximum hematocrit. Accordingly, the hematocrit–viscosity relation has often been represented by a Krieger-type asymptotic equation [10,45], . These forms describe the hematocrit–viscosity relationship over the full hematocrit range.
The major limitation in blood sample preparation is that the hematocrit intended from volumetric mixing is often different from the hematocrit obtained by a micro-hemocytometer. Considering that hematocrit strongly influences the viscosity of blood suspensions, hematocrit is commonly adjusted by centrifuging whole blood and recombining the concentrated red blood cell fraction with plasma or another suspending medium to obtain nominal target values [10]. However, the packed red blood cell layer obtained after centrifugation is not a pure cell phase because a small amount of plasma is trapped within the packed layer [46,47]. In addition, manual microhematocrit determination introduces reader-dependent variability and other measurement errors, which further complicate the accurate adjustment of hematocrit [48]. Therefore, when blood samples are prepared by pipetting fixed volumes of concentrated red blood cells and medium, the initially intended hematocrit may differ from the measured value, making post-preparation verification and repeated readjustment essential for obtaining a precise target hematocrit. This is especially important in viscosity experiments, where even small hematocrit deviations can alter the measured hematocrit–viscosity relationship [49]. To minimize hematocrit mismatch during sample preparation, the packed RBC fraction is washed two or three times to reduce residual plasma. The prepared suspension is verified using a standardized hematocrit method, and the mixing ratio is then readjusted on the basis of the measured hematocrit rather than the nominal volumetric value [13,14,50]. More recently, hematocrit has been measured by detecting the interface position in a capillary channel [9,51].
In this study, a new method is proposed to identify the full hematocrit–viscosity curve from three hematocrit–viscosity datasets based on the K–D regression model. First, the hematocrit of suspended blood is measured using a centrifuge hemocytometer and is denoted as ϕ1. Its corresponding viscosity (μ1) is measured by flowing the sample through a microfluidic chip. Next, centrifugation of the driving syringe separates the blood into RBC-rich and RBC-depleted layers. The hematocrit of the RBC-rich layer is measured as (ϕ2), while the viscosities of the RBC-rich and RBC-depleted layers are obtained as μ2 and μ3, respectively. The hematocrit of the RBC-depleted layer is assumed to be ϕ3 = 0. Finally, based on the K–D regression model as , the full hematocrit–viscosity curve is determined from the three hematocrit–viscosity datasets (i.e., ϕ1-μ1, ϕ2-μ2, and ϕ3-μ3).
Compared with the conventional method that requires multiple separately prepared blood samples at different hematocrit levels, the proposed method offers several advantages. First, it reduces repeated hematocrit adjustment by reconstructing the full hematocrit–viscosity curve from only three datasets. Second, it simplifies the experimental procedure by generating RBC-rich and RBC-depleted fractions directly from a single sample. Third, it decreases blood consumption, preparation time, and inter-sample variability, thereby providing a more efficient and consistent approach for identifying the full hematocrit–viscosity relationship.
2. Materials and Methods
2.1. Measurement of Hematocrit and Blood Viscosity
To obtain full hematocrit–viscosity curve, it was necessary to get hematocrit and blood viscosity, respectively.
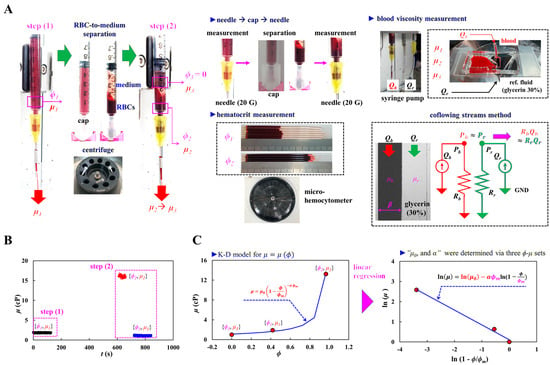
As shown in Figure 1A, an experimental setup was composed of a micro-hemocytometer for hematocrit (ϕ) and a microfluidic system for blood viscosity (μ). As shown in the left-side panel, procedures for measuring hematocrit and blood viscosity were divided into two steps. At the first step, with regard to suspended blood, hematocrit of suspended blood was obtained as ϕ1. The blood was loaded into a driving syringe. The viscosity of the suspended blood was obtained as μ1 by supplying the blood into a microfluidic chip. The needle (20 G) was removed from the syringe, and the syringe end was sealed with a plastic cap. The syringe was placed in a centrifuge (Allegra X-30, Beckman CoulterTM, Brea, CA, USA) and rotated at 4000 rpm for 10 min. After centrifugation, suspended blood was separated into an RBC-rich layer and RBC-depleted layer (i.e., medium) within the syringe. In the second step, the plastic cap was removed from the syringe, and a needle was attached to the syringe. The blood collected in the plastic cap was then used to determine the hematocrit of the RBC-rich blood (ϕ2). The syringe was mounted on a syringe pump. By operating the syringe pumps, both types of blood (i.e., RBC-rich blood and RBC-depleted blood) were delivered sequentially into a microfluidic chip. The corresponding viscosities of RBC-rich blood and RBC-depleted blood were then obtained as μ2 and μ3, respectively. For simplicity, the hematocrit of the RBC-depleted blood was assumed to be ϕ3 = 0.
Figure 1.
A proposed method for obtaining the full hematocrit–viscosity curve. (A) Experimental setup including the micro-hemocytometer for hematocrit (ϕ) and a microfluidic system for blood viscosity (μ). The left-side panel shows a two-step measurement of hematocrit and viscosity. The middle-side panel shows replacement of a syringe needle for RBC-to-medium separation and a micro-hemocytometer for hematocrit measurement. The right-side panel shows blood viscosity measurement using the coflowing streams method. (B) Time-lapse blood viscosity was obtained through two steps of measurement. (C) Calculation procedure of full hematocrit–viscosity curve using K-D regression model. The left-side panel shows the full hematocrit–viscosity curve using the K-D model: . Three hematocrit–viscosity datasets are plotted on the hematocrit (ϕ) and viscosity (μ) axes. The right-side panel shows linear regression analysis for obtaining two unknown variables (i.e., μ0 and α), where the ϕm is specified as ϕm = 1. The regression analysis estimated two unknown constants.
As shown in the middle panel of Figure 1A, a needle was attached to a syringe tip for blood viscosity measurements. The needle was replaced by a plastic cap for separating the suspended blood with a centrifuge. Using a micro-hemocytometer (VS-18000, Vison Science, Daejeon, Republic of Korea), the corresponding hematocrit values of the suspended blood and RBC-rich blood were determined as ϕ1 and ϕ2, respectively.
The right-side panel represents the blood viscosity measurement using the coflowing streams method [52,53,54]. To measure blood viscosity in the microfluidic environment, a microfluidic chip consisted of two inlets, a straight channel (width [w] = 1000 μm, length (L) = 14 mm) and an outlet. As shown in Figure 1A, blood was loaded through the inlet formed at the upper position of the channel. Reference fluid was supplied through the inlet formed at the side position of the channel. Based on microfabrication procedures (i.e., photo-lithography and soft-lithography), a polydimethylsiloxane (PDMS) block was replicated from a silicon master mold. Two inlets were formed using a biopsies punch (outer diameter = 0.75 mm). The PDMS block was bonded on a glass substrate using plasma treatment. To increase the bonding strength substantially, it was exposed to a hot plate of 140 °C for 30 min [55]. After test blood and reference fluid were loaded into each syringe, both syringes were positioned in two syringe pumps. Herein, a glycerin solution (30%) was selected as the reference fluid. As the flow rate of each fluid was set to Qb (blood) and Qr (reference fluid), both fluids were delivered into a microfluidic chip. To accurately detect blood viscosity, the interface between the two fluids was relocated near the middle width of the channel (β = 0.5) by adjusting the flow rate of the reference fluid. For simple mathematical representation, both streams in a single channel were mathematically represented using a discrete fluidic circuit model, which consisted of the flow rate (Qb, Qr) and fluidic resistance (Rb: fluidic resistance of blood; Rr: fluidic resistance of reference fluid). As each stream had the same pressure in a straight channel, the pressure relation between each stream was derived as Pb. The Pr and Pb were expressed as Pr = Rr × Qr and Pb = Rb × Qb. Using the same pressure condition of each stream (i.e., Rr × Qr ≈ Rb × Qb) [52], the viscosity formula of blood (μb) was derived as . Herein, the μr denotes the viscosity of the reference fluid.
As shown in Figure 1B, time-lapse blood viscosity was measured through a two-step procedure. Herein, control blood (ϕvol = 0.5) was prepared by adding normal RBCs (500 μL) into 1× PBS (500 μL). The flow rate of the control blood was set to Qb = 5 mL/h. In the first step, the hematocrit and viscosity of the suspended blood was quantified as ϕ1 = 0.44 ± 0.01 (n = 4) and μ1 = 2.02 ± 0.11 cP (n = 124), respectively. In the second step, the corresponding hematocrit–viscosity of the RBC-rich blood was obtained as ϕ2 = 0.97 ± 0.01 (n = 4) and μ2 = 17.19 ± 3.25 cP (n = 47). The viscosity of RBC-depleted blood was measured as μ3 = 1.24 ± 0.0 7 cP (n = 117).
To find out the regression coefficients of the K-D model, as shown in the left-side panel of Figure 1C, three hematocrit–viscosity datasets are plotted on the hematocrit (ϕ) axis and viscosity (μ) axis. According to the K-D regression model as , three unknown coefficients should be identified to get the full hematocrit–viscosity curve. Herein, if the ϕm was assumed as Qm = 1, the remaining two unknown coefficients (i.e., μ0 and α) could be obtained using linear regression analysis. In the K–D model, the α could be interpreted as an effective parameter representing the sensitivity of viscosity to hematocrit, analogous to an intrinsic-viscosity-related contribution in suspension theory. For blood samples, the α should be regarded as a semi-empirical parameter reflecting the combined effects of RBC properties and intercellular interactions. By taking the natural logarithm of both sides of the K–D model, the K-D regression formula could be rewritten in linearized form as ln (μ) = ln (μ0) − αϕm × ln (1 − ϕ/ϕm). Horizontal and vertical axes were defined as ln (1 − ϕ/ϕm) and ln (μ). As shown in right-side panel of Figure 1C, three hematocrit–viscosity datasets were then mapped onto the horizontal and vertical axes. According to linear regression analysis, two unknown coefficients (μ0, α) could be estimated accurately. That is, a full hematocrit–viscosity curve could be obtained using three hematocrit–viscosity datasets.
2.2. Blood Sample Preparation
Concentrated erythrocytes were provided by the Gwangju–Chonnam Blood Bank (Gwangju, Republic of Korea) and kept refrigerated until use in the experiment. Based on the established washing method described previously [56], normal RBCs were collected by repeatedly removing the supernatant suspension medium and buffy coat.
First, to determine how hematocrit affects blood viscosity, test suspensions were prepared by mixing normal RBCs with 1× PBS to obtain RBC volume fractions (ϕvol) between 10% and 100%. Second, to further examine the effect of the suspending medium, normal RBCs at a constant volume fraction (ϕvol = 0.5) were suspended in dextran solutions (Cdex = 5~30 mg/mL). The dextran solutions were made by dissolving dextran powder (Leuconostoc spp., MW 450–650 kDa, Sigma-Aldrich, St. Louis, MO, USA) in 1× PBS. Lastly, the effect of RBC rigidity on blood viscosity was investigated by modulating cell stiffness with glutaraldehyde treatment. Two glutaraldehyde concentrations (CGA = 0.075% and 0.15%) were prepared by diluting a 25% aqueous glutaraldehyde stock solution (Grade II, Sigma-Aldrich, USA) into 1× PBS. Normal RBCs were incubated in each glutaraldehyde solution with stirring for 10 min. Following centrifugation, the fixed RBCs were collected after removal of the supernatant PBS. The final test suspensions were then obtained by resuspending the hardened RBCs into 1× PBS.
2.3. Statistical Analysis
Data analysis was conducted using MINITAB software (Version 22.4, Minitab Inc., State College, PA, USA) and Microsoft Excel (Version 365, Microsoft, Redmond, WA, USA). Under the assumption of normality, all measurements were expressed as mean () ± standard deviation (σ). Number of data was denoted as n; 95% confidence intervals (CIs) (confidence interval) were determined from to . Differences among groups were assessed using one-way ANOVA, and statistical significance was accepted at a p-value < 0.05. Linear regression analysis was further performed in Microsoft Excel, and the resulting slope and intercept were used to calculate two unknown coefficients of the K-D regression model.
3. Results and Discussion
3.1. Determination of Maximum Packing Volume Fraction (ϕm) in the K-D Regression Model
In this subsection, the maximum packing volume fraction (ϕm) in the K–D regression model was determined by carefully evaluating the regression error using the root-mean-square (RMS) value. Two previously reported datasets were used to identify the best-fitted curve and the corresponding RMS as a function of ϕm.
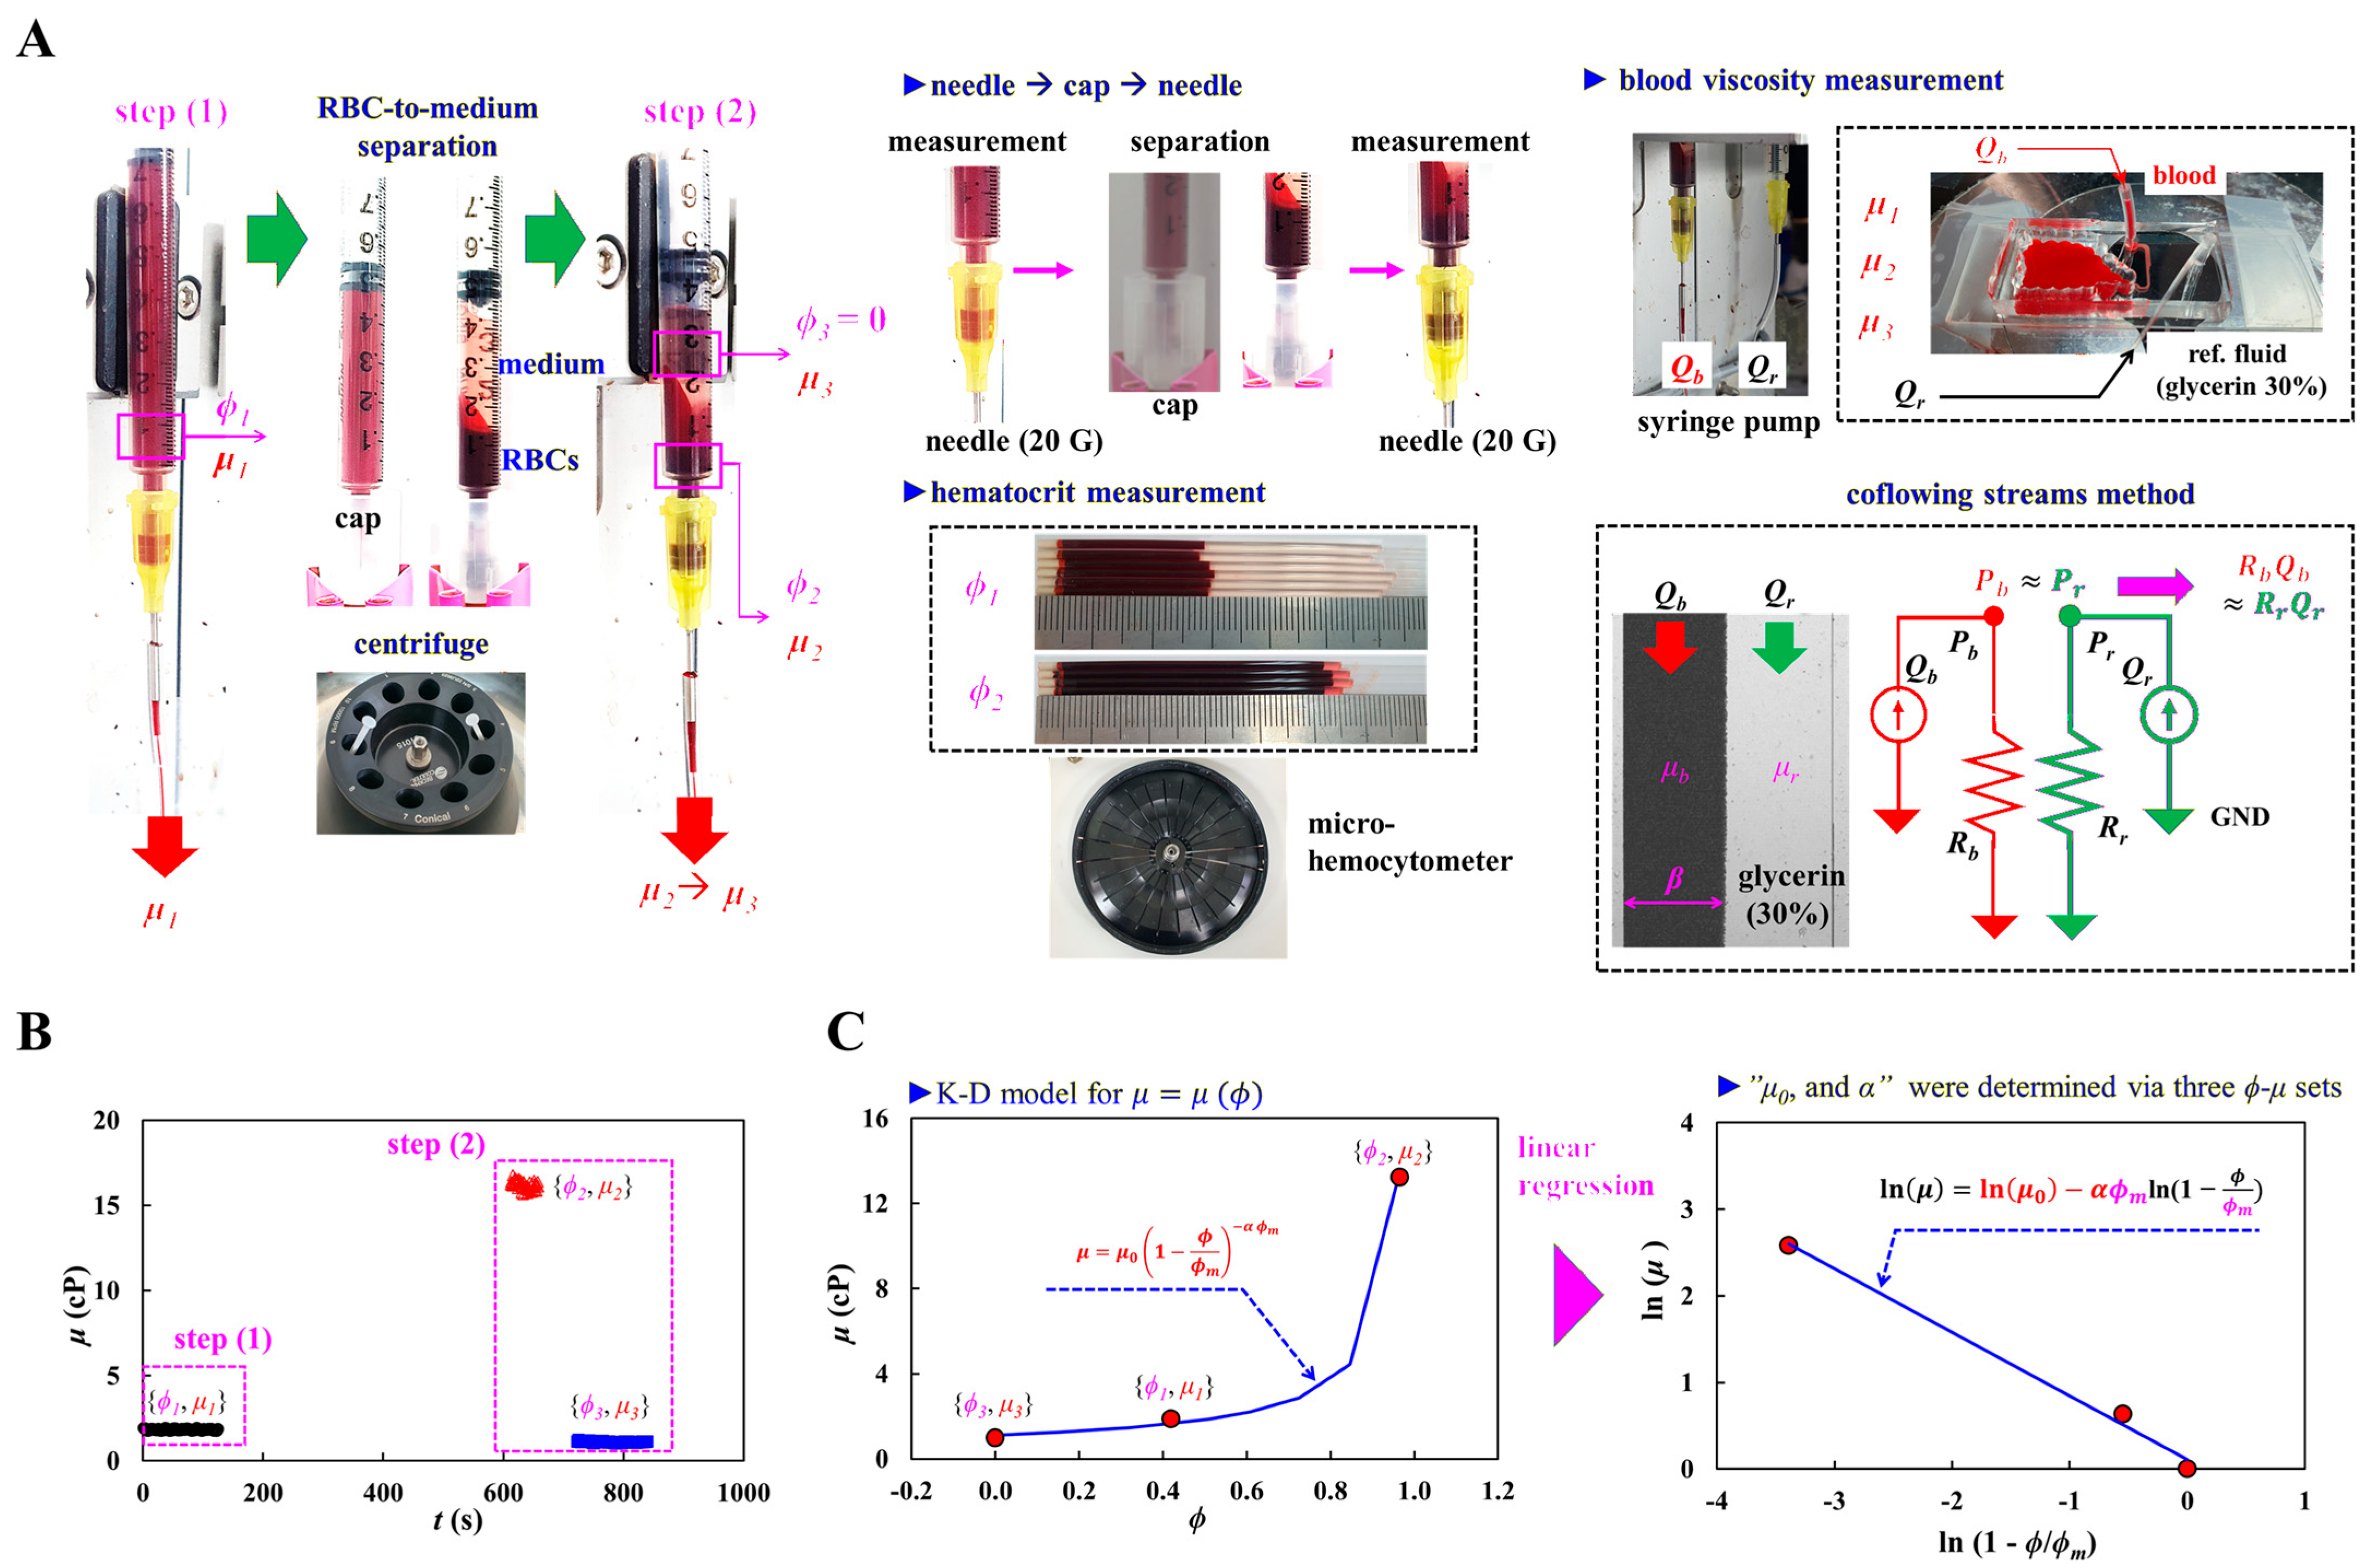
First, using hematocrit–viscosity data taken from reference (Pirofsky) [57], as shown in Figure 2(Ai), viscosity (μ) and (ϕ) are plotted along the horizontal and vertical axes, respectively. The red line represents the best-fitted curve determined by linear regression analysis. Figure 2(Aii) shows the best-fitted curve with respect to ϕm = 1.0 and 0.8. Herein, the horizontal and vertical axes were defined as ln (1 − ϕ/ϕm) and ln (μ), respectively. Hematocrit–viscosity datasets are plotted along both axes. According to the linear regression analysis, the corresponding formular of each ϕm was obtained as ln (μ) = −1.3047 ln (1 − ϕ/ϕm) + 0.1776 (R2 = 0.9176) for ϕm = 1.0 and ln (μ) = −0.6384 ln (1 − ϕ/ϕm) + 0.3933 (R2 = 0.8801) for ϕm = 0.8. That is, the corresponding αϕm of each ϕm was obtained as αϕm = −1.3047 (ϕm = 1.0) and αϕm = −0.6387 (ϕm = 0.8). In addition, the corresponding μ0 of each ϕm was obtained as μ0 = 1.194 cP (ϕm = 1.0) and μ0 = 1.482 cP (ϕm = 1.0). As the coefficient of R2 was obtained as high value of R2 = 0.8801~0.9176, both best-fitted curves represented variations in μ with respect to ϕ sufficiently. As shown in Figure 2(Aiii), the raw data and best-fitted curves are superimposed along the hematocrit (ϕ) and viscosity (μ) axes, respectively, where blue and pink lines represent the best-fitted curves obtained by assuming ϕm = 0.8 and ϕm = 1.0, respectively. The results suggest that the best-fitted curve obtained by assuming ϕm = 1.0 was more accurate than that obtained by assuming ϕm = 0.8. To assess the effect of ϕm on the accuracy of the regression analysis, multiple data points of ϕm were selected between 0.8 and 1.0.
Figure 2.
Determination of ϕm for the K-D regression model using the hematocrit–viscosity set taken from two studies. (A) The impact of ϕm on the accuracy of the regression model using hematocrit–viscosity sets taken from the literature (Pirofsky [57]). (i) Variations in blood viscosity (μ) with respect to hematocrit (ϕ). The red curve represents the best-fitted curve of the K-D regression model. (ii) Linear curve-fitting procedure with respect to ϕm = 1.0 and 0.8. (iii) Comparison of a curve-fitting formula with respect to ϕm. The blue and pink lines denote the best-fitted curve obtained by assuming ϕm = 0.8 and 1.0. (iv) Variations in αϕm and μ0 with respect to ϕm. (v) Variations in root-mean-square value of μ (μrms) with respect to ϕm. (B) The effect of ϕm on K-D model accuracy using hematocrit–viscosity data taken from the literature (Lacombe et al. [58]). (i) Variations in μ with respect to ϕ. (ii) Linear curve-fitting procedure with respect to ϕm = 1.0 and 0.8. According to the linear regression analysis, the corresponding formula of each ϕm was obtained as ln (μ) = −1.5087 ln (1 − ϕ/ϕm) + 0.6691 (R2 = 0.988) for ϕm = 1.0 and ln (μ) = −0.9601 ln (1 − ϕ/ϕm) + 0.7589 (R2 = 0.8801) for ϕm = 0.8. (iii) Comparison of the best-fitted curve with respect to ϕm = 0.8 and 1.0. (iv) Variations in αϕm and μ0 with respect to ϕm. (v) Variations in μrms with respect to ϕm.
As shown Figure 2(Aiv), linear regression analysis yielded the changes in αϕm and μ0 as a function of ϕm. According to the results, as ϕm increased from 0.8 to 1.0, αϕm and μ0 tended to decrease gradually, confirming that the ϕm had a strong impact on determination on both coefficients. In addition, to evaluate the accuracy of the regression analysis, the root-mean-square (RMS) value of μ (i.e., μrms) was calculated with respect to ϕm. Herein, the μrms represented the average deviation between measured and predicted values (i.e., ; μi: measured viscosity and : predicted viscosity). As shown in Figure 2(Av), the variations in μrms are plotted as a function of ϕm. The results indicated that a higher value of ϕm led to a substantial decrease in μrms. Accordingly, the most accurate curve fitting was obtained when ϕm was set to 1.0.
Second, hematocrit–viscosity data taken from the literature (Lacombe et al.) [58] was additionally used to validate the contribution of ϕm to the accuracy of the regression analysis. Figure 2(Bi) depicts all hematocrit–viscosity datasets and the best-fitted curve of the K-D regression model. As shown in Figure 2(Bii), according to the linear regression analysis, the best-fitted curve was obtained by assuming ϕm = 1.0 and ϕm = 0.8. As a result, the corresponding formula of each ϕm was obtained as ln (μ) = −1.5087 ln (1 − ϕ/ϕm) + 0.6691 (R2 = 0.988) for ϕm = 1.0, and ln (μ) = −0.9601 ln (1 − ϕ/ϕm) + 0.7589 (R2 = 0.8801) for ϕm = 0.8. That is, the corresponding αϕm of each ϕm was estimated as αϕm = −1.5087 (ϕm = 1.0) and αϕm = −0.9601 (ϕm = 0.8). Additionally, the corresponding μ0 of each ϕm was estimated as μ0 = 1.952 cP (ϕm = 1.0) and μ0 = 2.136 cP (ϕm = 0.8). To validate the accuracy of the best-fitted curve, as shown in Figure 2(Biii), experimental datasets and both regression curves were superimposed on the hematocrit (ϕ) and viscosity (μ) axes. The results indicated that both best-fitted curves were well matched with the experimental datasets. To investigate the contribution of ϕm to the coefficients (i.e., αϕm and μ0), multiple values of ϕm were selected between 0.8 and 1.0. As shown in Figure 2(Biv), variations in αϕm and μ0 were obtained with respect to ϕm. The results indicated that the ϕm contributed to decreasing both coefficients substantially. Specifically, the ϕm had a strong influence on the determination of αϕm and μ0. As shown in Figure 2(Bv), to validate the accuracy of the best-fitted curve, variations in μrms were obtained with respect to ϕm. According to the results, the μrms tended to decrease gradually at a higher value of ϕm. Thus, it is necessary to set ϕm = 1.0 for getting a more accurate best-fitted curve.
From the curve-fitting analysis of two kinds of previous hematocrit–viscosity datasets, the maximum packing volume fraction (ϕm) in the K–D regression model had a strong influence on the determination of αϕm and μ0. Additionally, the root-mean-square value of the best-fitted curve was minimized at a higher value of ϕm = 1.0. Based on the simulation study, the study adopted ϕm = 1.0 for getting a best-fitted curve of the hematocrit–viscosity datasets.
From the curve-fitting analysis of two previously reported hematocrit–viscosity datasets, the maximum packing volume fraction (ϕm) in the K–D regression model was found to strongly affect the determination of αϕm and μ0. In addition, the root-mean-square error of the fitted curve was minimized when a higher value of ϕm = 1.0 was used. Based on this simulation analysis, ϕm = 1.0 was adopted to obtain the best-fitted hematocrit–viscosity curve.
3.2. Hematocrit–Viscosity Measurement Datasets of Control Blood
In this subsection, with regard to control blood, full hematocrit–viscosity datasets were obtained at higher shear rates (i.e., > s−1). Herein, the control blood was prepared by adding normal RBCs into 1× PBS.
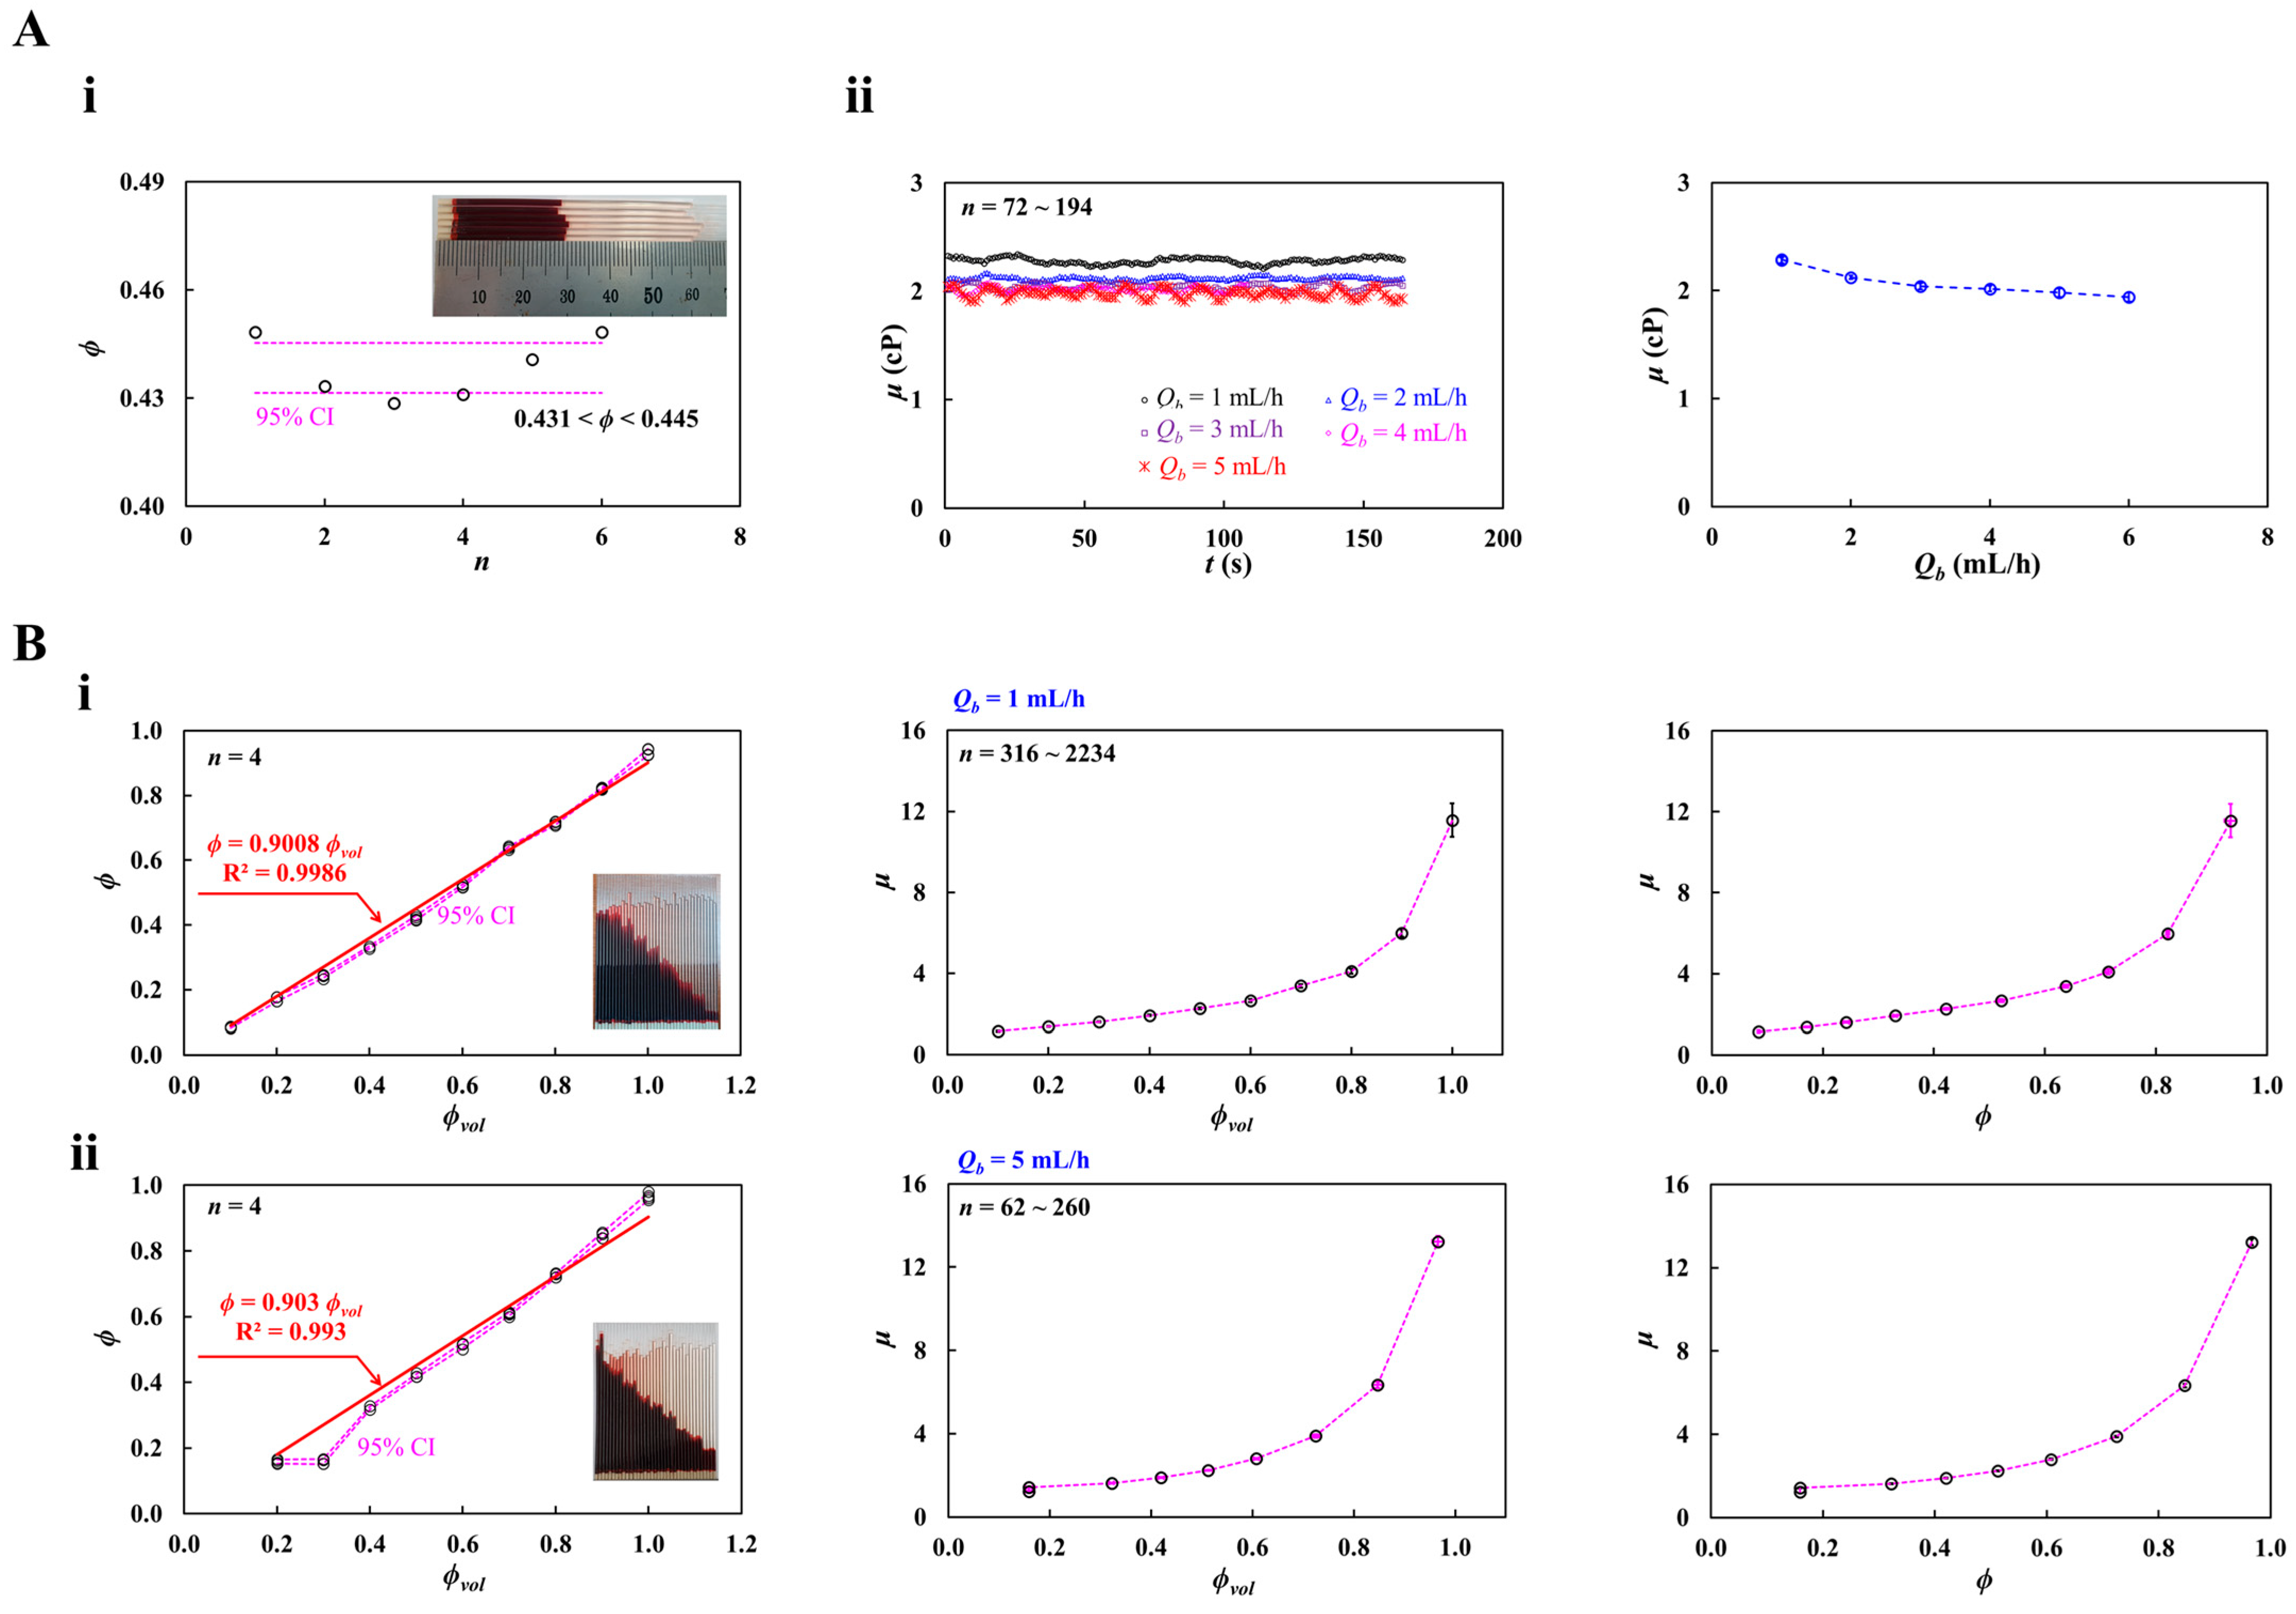
First, to determine the appropriate blood flow rate of the syringe pump (Qb), blood viscosity (μ) was measured over a flow rate ranging from Qb = 1 mL/h to Qb = 5 mL/h. Following the previously reported coflowing streams method [52], the reference-fluid flow rate (Qr) was adjusted so that the interface was positioned near the center of the channel width. The RBC volume fraction in the blood was set to ϕvol = 0.5. As shown in Figure 3(Ai), six control blood samples (Sn = 6) were set to probe the variation in hematocrit (ϕ). The inset exhibits capillary tubes used for measuring hematocrit. Dashed lines represent the 95% CI (i.e., 0.431 < ϕ < 0.445). Next, the blood viscosity of control blood was obtained with respect to Qb. To relocate the interface near the center of the channel width, with respect to Qb, the corresponding flow rate of the reference fluid was set to Qr = 1 mL/h (Qb = 1 mL/h), Qr = 2 mL/h (Qb = 2 mL/h), Qr = 2.5 mL/h (Qb = 3 mL/h), Qr = 4 mL/h (Qb = 4 mL/h), Qr = 4.2 mL/h (Qb = 5 mL/h), and Qr = 5 mL/h (Qb = 6 mL/h). The corresponding interface of both flow rate conditions was measured as β = 0.460 ± 0.004 (Qb = 1 mL/h, Qr = 1 mL/h), β = 0.442 ± 0.002 (Qb = 2 mL/h, Qr = 2 mL/h), β = 0.477 ± 0.003 (Qb = 3 mL/h, Qr = 2.5 mL/h), β = 0.462 ± 0.003 (Qb = 4 mL/h, Qr = 4 mL/h), β = 0.468 ± 0.005 (Qb = 5 mL/h, Qr = 4.2 mL/h), and β = 0.464 ± 0.005 (Qb = 6 mL/h, Qr = 5 mL/h). As shown in the left-side panel of Figure (3Aii), the blood viscosity of control blood was obtained with respect to Qb. The corresponding viscosity of each flow rate was obtained as μ = 2.29 ± 0.03 cP (n = 164, Qb = 1 mL/h), μ = 2.12 ± 0.02 cP (n = 189, Qb = 2 mL/h), μ = 2.04 ± 0.03 cP (n = 194, Qb = 3 mL/h), μ = 2.02 ± 0.03 cP (n = 108, Qb = 4 mL/h), μ = 1.98 ± 0.04 cP (n = 181, Qb = 5 mL/h), and μ = 1.94 ± 0.04 cP (n = 74, Qb = 6 mL/h). Based on the shear rate formula [52] (i.e., , the corresponding shear rate of each blood flow rate was estimated as =1451.5 s−1 (Qb = 1 mL/h), = 3020 s−1 (Qb = 2 mL/h), = 4194.1 s−1 (Qb = 3 mL/h), = 5773.2 s−1 (Qb = 4 mL/h), = 7130.1 s−1 (Qb = 5 mL/h), and = 8617.7 s−1 (Qb = 6 mL/h). The right-side panel of Figure 3(Aii) exhibits variations in blood viscosity with respect to Qb. Blood viscosity decreased substantially over Qb = 1~3 mL/h, whereas only a slight decrease was observed over Qb = 3~6 mL/h. Based on these results, Qb = 1 and 5 mL/h were selected for measuring blood viscosity at higher shear rates.
Figure 3.
Experimental measurement of the hematocrit–viscosity datasets of control blood at a high shear rate. The control blood was prepared by adding normal RBCs into 1× PBS. (A) Determination of blood flow rate (Qb). Herein, the RBC volume fraction in the blood was set to ϕvol = 0.5. (i) Variations in hematocrit (ϕ) for six control blood samples (Sn = 6). The dashed line denotes 95% confidential intervals (i.e., 0.431 < ϕ < 0.445). (ii) Variations in μ with respect to the blood flow rate (Qb). The left-side panel shows time-lapse viscosity with respect to Qb ranging from Qb = 1 mL/h to Qb = 6 mL/h. The right-side panel shows variations in μ with respect to Qb. The error bar represents the standard deviation. (B) Measurement of hematocrit–viscosity datasets at Qb = 1 and 5 mL/h. (i) Measurement of ϕ-μ obtained at Qb = 1 mL/h. The left-side panel shows the relationship between ϕ and ϕvol. The dashed line exhibits the 95% CI. The mid-side panel exhibits variations in μ with respect to ϕvol. The error bar denotes the standard deviation. The right-side panel shows variations in μ with respect to ϕ. The error bar represents the standard deviation. (ii) Measurement of ϕ-μ obtained at Qb = 5 mL/h. The left-side panel shows the relationship between ϕ and ϕvol. The dashed line exhibits the 95% CI. The mid-side panel exhibits variations in μ with respect to ϕvol. The error bar denotes the standard deviation. The right-side panel shows variations in μ with respect to ϕ. The error bar represents standard deviation.
Second, hematocrit–viscosity datasets were obtained at Qb = 1 and 5 mL/h. As shown in Figure 3(Bi), the hematocrit–viscosity datasets were obtained at Qb = 1 mL/h. The left-side panel shows the relationship between ϕ and ϕvol. Herein, the ϕvol of control blood was adjusted to ϕvol = 0.1~1.0. The corresponding hematocrit of each type of blood was obtained with a micro-hemocytometer. The dashed line exhibits the 95% CI. The inset shows representative images used to determine the RBC volume fraction (ϕ) in a microcapillary tube following centrifugation. According to the linear regression analysis, the best-fitted curve was obtained as ϕ = 0.908 ϕvol (R2 = 0.9986). The middle-side panel exhibits variations in μ with respect to ϕvol. The number of viscosity data at each ϕvol ranged from n = 316 to n = 2234. The right-side panel shows variations in μ with respect to ϕ. The corresponding viscosity of each hematocrit was obtained as μ = 1.14 ± 0.03 cP (ϕ = 0.08 ± 0.002), μ = 1.37 ± 0.03 cP (ϕ = 0.17 ± 0.006), μ = 1.60 ± 0.04 cP (ϕ = 0.24 ± 0.006), μ = 1.92 ± 0.05 cP (ϕ = 0.33 ± 0.004), μ = 2.26 ± 0.05 cP (ϕ = 0.42 ± 0.007), μ = 2.66 ± 0.08 cP (ϕ = 0.52 ± 0.005), μ = 3.38 ± 0.08 cP (ϕ = 0.64 ± 0.005), μ = 4.10 ± 0.12 cP (ϕ = 0.71 ± 0.006), μ = 5.99 ± 0.18 cP (ϕ = 0.82 ± 0.003), and μ = 11.56 ± 0.83 cP (ϕ = 0.93 ± 0.011). On the other hand, as shown in Figure 3(Bii), hematocrit–viscosity datasets were obtained at Qb = 5 mL/h. The left-side panel shows the relationship between ϕ and ϕvol. According to the linear regression analysis, the best-fitted curve was obtained as ϕ = 0.903 ϕvol (R2 = 0.993). The middle-side panel exhibits variations in μ with respect to ϕvol. The number of viscosity data at each ϕvol ranged from n = 52 to n = 260. The right-side panel shows variations in μ with respect to ϕ. The corresponding viscosity of each hematocrit was obtained as μ = 1.24 ± 0.02 cP (ϕ = 0.16 ± 0.006), μ = 1.43 ± 0.02 cP (ϕ = 0.16 ± 0.007), μ = 1.63 ± 0.02 cP (ϕ = 0.32 ± 0.004), μ = 1.89 ± 0.03 cP (ϕ = 0.42 ± 0.006), μ = 2.24 ± 0.03 cP (ϕ = 0.51 ± 0.008), μ = 2.80 ± 0.04 cP (ϕ = 0.61 ± 0.006), μ = 3.89 ± 0.08 cP (ϕ = 0.72 ± 0.007), μ = 6.34 ± 0.16 cP (ϕ = 0.85 ± 0.009), and μ = 13.23 ± 0.26 cP (ϕ = 0.97 ± 0.011).
Experimental measurements provided two hematocrit–viscosity datasets at Qb = 1 and 5 mL/h, which were used to validate the accuracy of the proposed method for reconstructing the full hematocrit–viscosity curve based on the K–D regression model.
3.3. Quantitative Evaluation of Proposed Method Using Hematocrit–Viscosity Datasets of Control Blood
In this subsection, as shown in Figure 3B, the proposed method for getting the full hematocrit–viscosity curve was validated using experimental data. Herein, with respect to each hematocrit, blood viscosity was obtained at Qb = 1 and 5 mL/h.
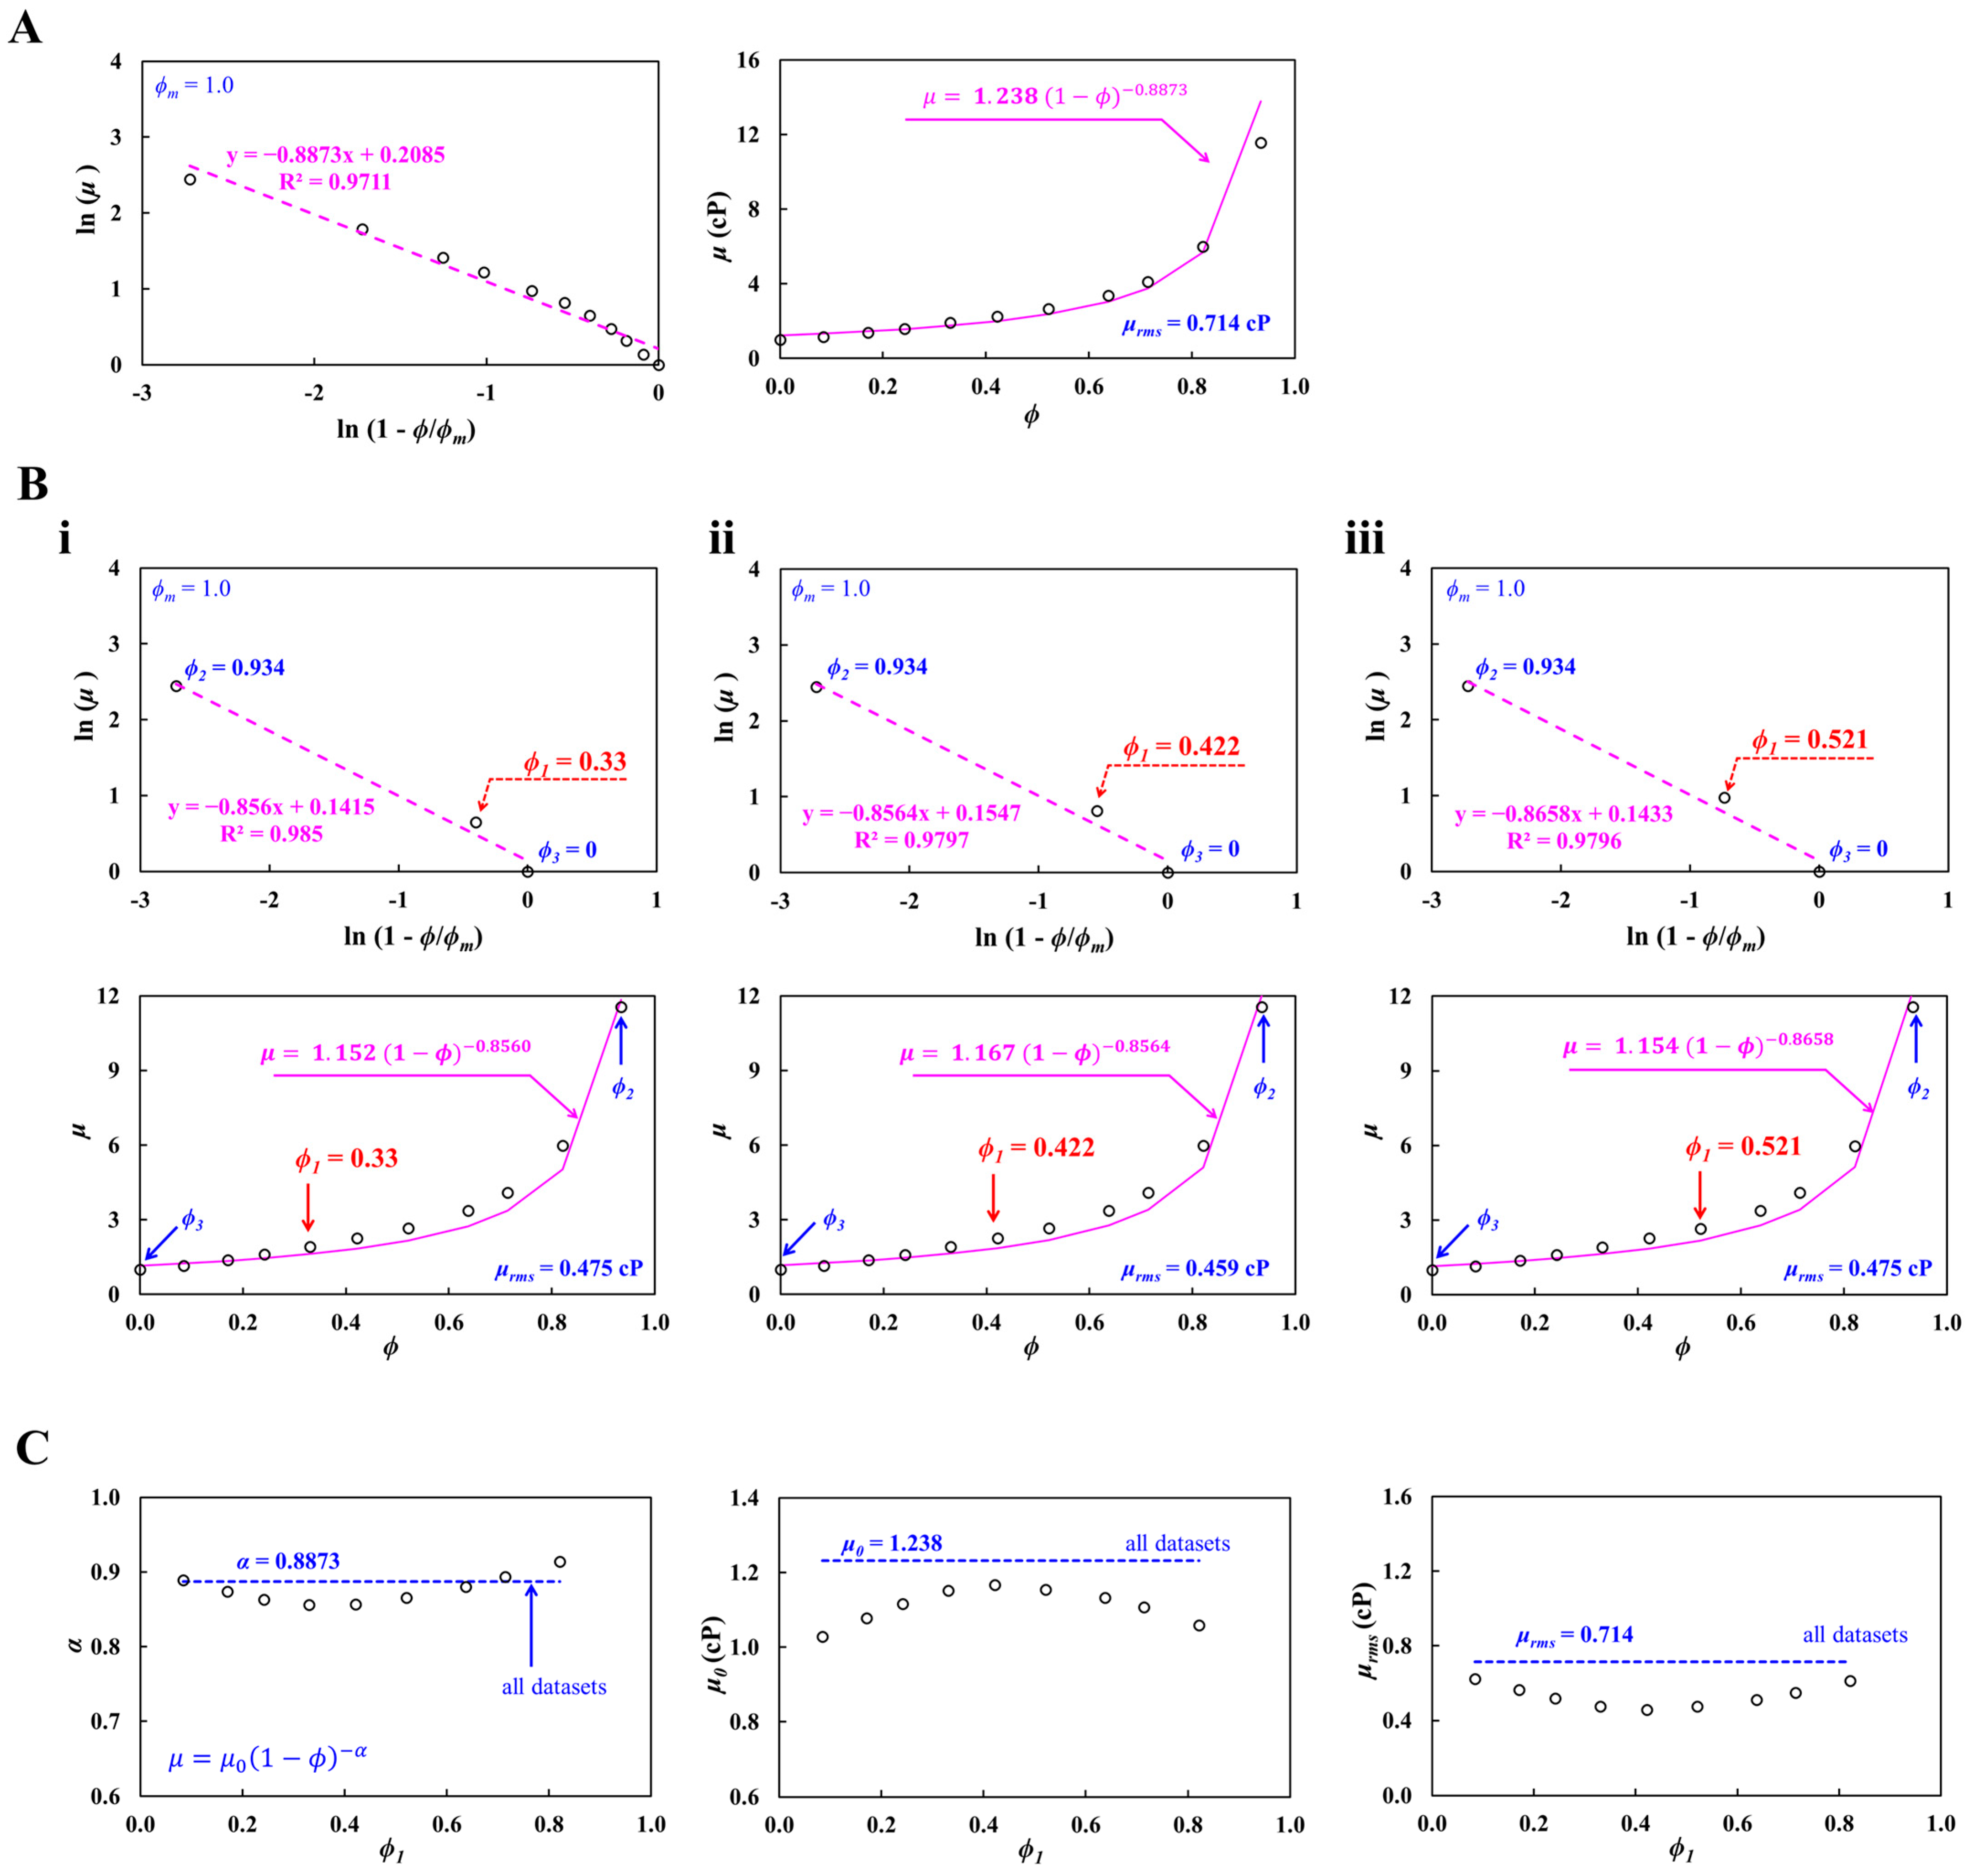
First, validation of proposed method was conducted using eleven hematocrit–viscosity datasets, where blood viscosity was measured at a flow rate of Qb = 1 mL/h (= 1451.5 s−1). Figure 4A represents the complete hematocrit–viscosity curve identification using eleven ϕ-μ datasets. Herein, the ϕm was set to ϕm = 1.0. As shown in the left-side panel, hematocrit–viscosity datasets are mapped on the ln (1 − ϕ/ϕm) and ln (μ) axes. According to the linear regression analysis, the best-fitted curve was obtained as ln (μ) = −0.8873 ln (1 − ϕ/ϕm) + 0.2085 (R2 = 0.9711). From the curve-fitting formula, αϕm and μ0 were obtained as αϕm = −0.8873 and μ0 = 1.238 cP, respectively. As shown in right-side panel, the best-fitted curve of is superimposed on all hematocrit–viscosity datasets. The results showed that the best-fitted curve was in good agreement with the experimental datasets, except at the highest hematocrit value of ϕ = 0.934. The root-mean-square error was estimated as μrms = 0.714 cP. Using all experimental datasets as shown in Figure 4A, the full hematocrit–viscosity curve was identified using three ϕ-μ datasets. Herein, both boundary datasets (i.e., ϕ2 = 0.934: μ2 = 11.56 cP and ϕ3 = 0: μ3 = 1 cP) were fixed during hematocrit–viscosity curve identification. The middle point dataset (ϕ1 = 0.08~0.82) was only selected from the remaining nine datasets. As show in Figure 4(Bi), the full hematocrit–viscosity curve was calculated using midpoint dataset (i.e., ϕ1 = 0.33, μ1 = 1.917 cP). According to the linear regression analysis, the best-fitted curve was obtained as ln (μ) = −0.856 ln (1 − ϕ) + 0.1415 (R2 = 0.985); α and μ0 were estimated as α = −0.856 and μ0 = 1.152 cP, respectively. The complete hematocrit–viscosity curve was then identified as . Additionally, root-mean-square error was estimated as μrms = 0.475 cP. Similarly, as shown in Figure 4(Bii), the full hematocrit–viscosity curve was estimated using the midpoint dataset (i.e., ϕ1 = 0.422, μ1 = 2.264 cP). According to the linear regression analysis, the best-fitted curve was obtained as ln (μ) = −0.8564 ln (1 − ϕ) + 0.1547 (R2 = 0.9797); α and μ0 were estimated as α = −0.8564 and μ0 = 1.167 cP, respectively. The complete hematocrit–viscosity curve was then identified as . The root-mean-square error was estimated as μrms = 0.459 cP. As shown in Figure 4(Biii), the full hematocrit–viscosity curve was calculated using the midpoint dataset (i.e., ϕ1 = 0.521, μ1 = 2.657 cP). According to the linear regression analysis, the best-fitted curve was obtained as ln (μ) = −0.8658 ln (1 − ϕ) + 0.1433 (R2 = 0.9796); α and μ0 were estimated as α = −8658 and μ0 = 1.154 cP, respectively. The full hematocrit–viscosity curve was then identified as . The root-mean-square error was estimated as μrms = 0.475 cP. Figure 4C exhibits a quantitative comparison of the full hematocrit–viscosity curve obtained by all datasets and three datasets selected from all datasets. The left-side panel exhibits variations in α with respect to the selected midpoint dataset (ϕ1). The dashed line represents α = 0.8873, obtained by all hematocrit–viscosity datasets. The value of α was strongly affected by the selected midpoint dataset. The mid-side panel shows variations in μ0 with respect to the selected midpoint dataset (ϕ1). The dashed line represents μ0 = 1.238 cP, obtained by all hematocrit–viscosity datasets. Considering that the blood viscosity at ϕ = 0 was measured as μ = 1.028 cP, the μ0 estimated from all hematocrit–viscosity datasets was overestimated by approximately 20.4%. Moreover, the μ0 values obtained from the three selected datasets were lower than those derived from the full dataset, with minimum values at low and high hematocrit and a maximum value near ϕ = 0.33–0.52. The right-side panels depict variations in μrms with respect to the midpoint dataset (ϕ1). The dashed line represents μrms = 0.714 cP obtained by all hematocrit–viscosity datasets. The proposed method using three selected datasets yielded a lower root-mean-square error than the conventional method using all datasets. In particular, when ϕ was selected between 0.33 and 0.52, the root-mean-square error was estimated as μrms = 0.475~0.495 cP. These results indicated that the full hematocrit–viscosity curve obtained from the three selected datasets was more accurate and remained in good agreement with the overall hematocrit–viscosity datasets.
Figure 4.
Validation of the proposed method using eleven hematocrit–viscosity sets, where blood viscosity was measured at a flow rate of Qb = 1 mL/h. (A) Complete hematocrit–viscosity curve identification using eleven ϕ-μ datasets. As shown in the left-side panel, hematocrit–viscosity datasets are mapped on the ln (1 − ϕ/ϕm) and ln (μ) axes. The right-side panel shows all hematocrit–viscosity datasets and their best-fitted curve of . (B) Regression formula using three ϕ-μ datasets. Herein, both boundary datasets (i.e., ϕ2 = 0.934: μ2 = 11.56 cP and ϕ3 = 0: μ3 = 1 cP) are fixed to get the complete hematocrit–viscosity curve. The middle point dataset (ϕ1) was selected from the remaining nine datasets. (i) Full hematocrit–viscosity curve using the midpoint dataset (i.e., ϕ1 = 0.33, μ1 = 1.917 cP). The complete hematocrit–viscosity curve and root-mean-square error were obtained as and μrms = 0.475 cP. (ii) Full hematocrit–viscosity curve using midpoint dataset (i.e., ϕ1 = 0.422, μ1 = 2.264 cP). Complete hematocrit–viscosity curve and root-mean-square error were estimated as and μrms = 0.459 cP. (iii) Full hematocrit–viscosity curve using midpoint dataset (i.e., ϕ1 = 0.521, μ1 = 2.657 cP). Full hematocrit–viscosity curve and root-mean-square error were calculated as and μrms = 0.475 cP. (C) Quantitative comparison of full hematocrit–viscosity curve obtained from all datasets (i.e., conventional method) and three selected datasets (i.e., proposed method). The dashed line represents α = 0.8873, μ0 = 1.238 cP, and μrms = 0.714 cP obtained from all hematocrit–viscosity datasets. The left-side panel exhibits variations in α with respect to the selected midpoint dataset (ϕ1). The mid-side panel shows variations in μ0 with respect to the selected midpoint dataset (ϕ1). The right-side panels depict variations in μrms with respect to the midpoint dataset (ϕ1).
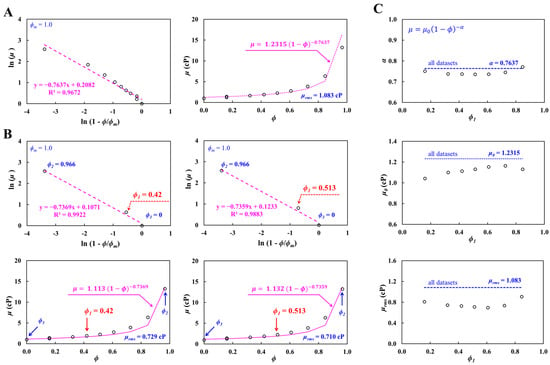
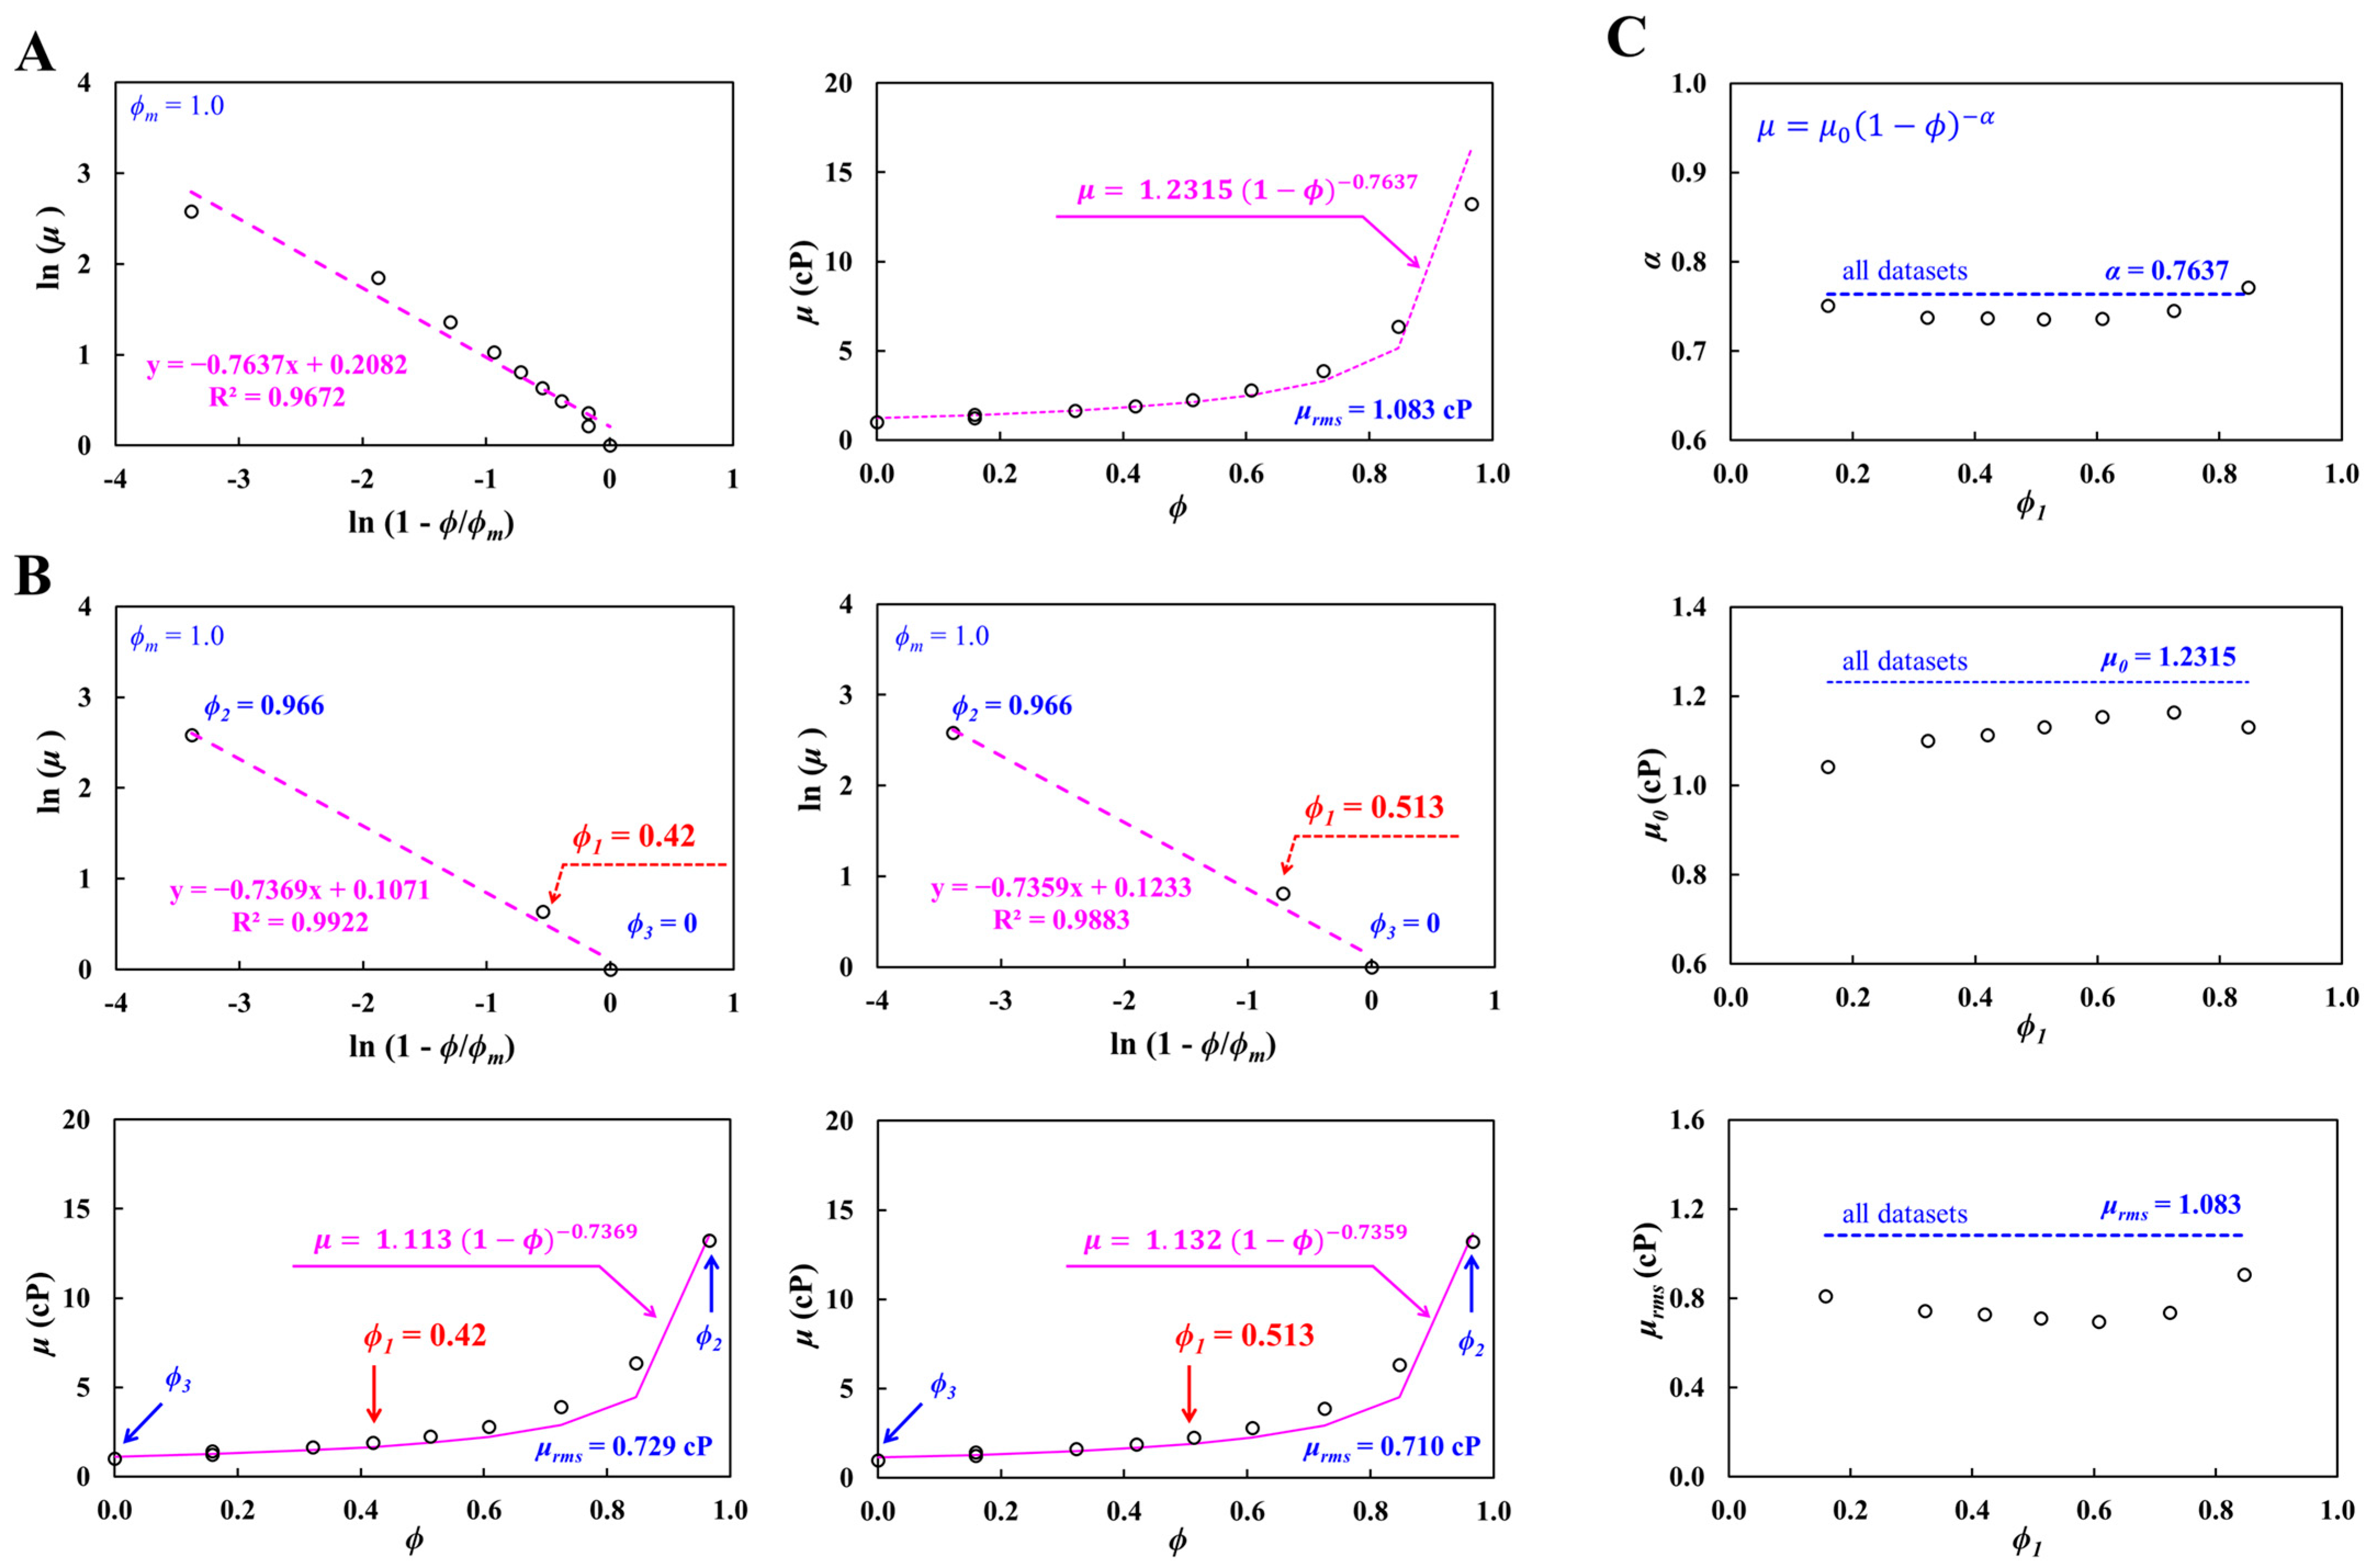
Second, the full hematocrit–viscosity curve was estimated using ten hematocrit–viscosity datasets, where blood viscosity was measured at Qb = 5 mL/h (= 7130.1 s−1). Figure 5A depicts the full hematocrit–viscosity curve obtained from ten ϕ-μ datasets. Herein, ϕm was set to ϕm = 1.0. As shown in the left-side panel, the linear regression analysis gave best-fitted curve as ln (μ) = −0.7637 ln (1 − ϕ) + 0.2082 (R2 = 0.9672); α and μ0 were then obtained as α = 0.7637 and μ0 = 1.2318 cP. As shown in the right-side panel, the full hematocrit–viscosity curve of was superimposed on all hematocrit–viscosity datasets. The results showed that the best-fitted curve was in satisfactory agreement with the experimental datasets. The root-mean-square error was estimated as μrms = 1.083 cP.
Figure 5.
Validation of proposed method using ten hematocrit–viscosity datasets, where blood viscosity was measured at Qb = 5 mL/h. (A) Full hematocrit–viscosity curve identification using ten ϕ-μ datasets. As shown in the left-side panel, linear regression analysis gave the best-fitted curved as ln (μ) = −0.7637 ln (1 − ϕ) + 0.2082 (R2 = 0.9672). As depicted in the right-side panel, the full hematocrit–viscosity curve of was superimposed on all hematocrit–viscosity datasets. Root-mean-square error was estimated as μrms = 1.083 cP. (B) Full hematocrit–viscosity curve identification using three ϕ-μ datasets. Herein, both boundary datasets (i.e., ϕ2 = 0.966: μ2 = 13.23 cP and ϕ3 = 0: μ3 = 1 cP) were fixed during the identification of the complete hematocrit–viscosity curve. First, with regard to the midpoint dataset (i.e., ϕ1 = 0.42, μ1 = 1.889 cP), the full hematocrit–viscosity curve and root-mean-square error were obtained as and μrms = 0.729 cP. Second, with regard to the midpoint dataset (i.e., ϕ1 = 0.513, μ1 = 2.245 cP), the full hematocrit–viscosity curve and root-mean-square error were obtained as and μrms = 0.71 cP. (C) Quantitative comparison of full hematocrit–viscosity curve obtained by all datasets and three datasets. The dashed line represents α = 0.7637, μ0 = 1.2315 cP, and μrms = 1.083 cP obtained from all hematocrit–viscosity datasets. Upper-side panel exhibits variations in α with respect to the midpoint dataset (ϕ1). The mid-side panel shows variations in μ0 with respect to the midpoint dataset (ϕ1). The lower-side panels depict variations in μrms with respect to the midpoint dataset (ϕ1).
As shown in Figure 5B, the full hematocrit–viscosity curve identification was obtained from the three selected ϕ-μ datasets. In the identification of the complete hematocrit–viscosity curve, both boundary datasets (i.e., ϕ2 = 0.966: μ2 = 13.23 cP and ϕ3 = 0: μ3 = 1 cP) were fixed. The midpoint dataset (ϕ1) was selected from the remaining eight datasets. As shown in left-side panel, with regard to the midpoint dataset (i.e., ϕ1 = 0.42, μ1 = 1.889 cP), the best-fitted curve was obtained as ln (μ) = −0.7369 ln (1 − ϕ) + 0.1071 (R2 = 0.9922); α and μ0 were then obtained as α = 0.7369 and μ0 = 1.113 cP. The full hematocrit–viscosity curve and root-mean-square error were obtained as and μrms = 0.729 cP. As shown in the right-side panel, with regard to the midpoint dataset (i.e., ϕ1 = 0.513, μ1 = 2.245 cP), the best-fitted curve was obtained as ln (μ) = −0.7359 ln (1 − ϕ) + 0.1233 (R2 = 0.9883). The full hematocrit–viscosity curve and root-mean-square error were obtained as and μrms = 0.71 cP. As shown in Figure 5C, the coefficients of the K-D regression model (α, μ0) and root-mean-square error (μrms) are plotted as a function of the selected midpoint dataset (ϕ1). The dashed line represents α = 0.7637, μ0 = 1.2315 cP, and μrms = 1.083 cP obtained from all hematocrit–viscosity datasets. The upper-side panel exhibits variations in α with respect to the midpoint dataset (ϕ1). The results revealed a strong dependence of α on ϕ1. The mid-side panel shows variations in μ0 with respect to the midpoint dataset (ϕ1). The μ0 obtained from the three selected datasets was lower than that derived from the full dataset. The lower-side panels depict variations in μrms with respect to the midpoint dataset (ϕ1). According to the results, the μrms obtained from the three selected datasets was much lower than that derived from the full dataset.
From the identification of the full hematocrit–viscosity curve, the exponent of the K-D model was found to depend strongly on the midpoint dataset (ϕ1, μ1). The μ0 and μrms values obtained from the three selected datasets were substantially lower than those obtained from all the hematocrit–viscosity datasets. Although the high-hematocrit condition of the RBC-rich blood was beyond the normal physiological range, it was intentionally included as an upper-bound condition generated by centrifugation to provide a boundary dataset for K–D model fitting and to improve reconstruction of the full hematocrit–viscosity relationship. Therefore, the full hematocrit–viscosity curve reconstructed from the three selected datasets could be considered more accurate when compared with the full hematocrit–viscosity curve obtained from all the hematocrit–viscosity curves.
3.4. Contribution of Suspending Medium to Full Hematocrit–Viscosity Curve
In this subsection, to evaluate the contribution of the suspending medium to the full hematocrit–viscosity curve [45,59], a specific concentration of a dextran solution (Cdex = 0~30 mg/mL) was prepared as the blood medium. Herein, Cdex = 0 denoted 1× PBS. Test blood (ϕvol = 0.5) was then prepared by adding normal RBCs into a specific concentration of the dextran solution. Blood viscosity was obtained at a flow rate of 5 mL/h.
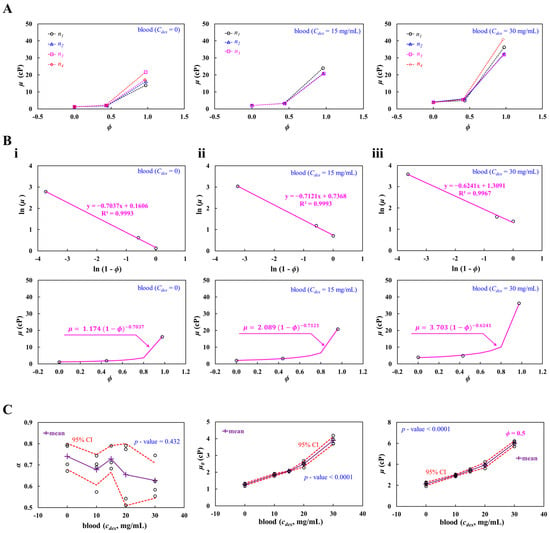
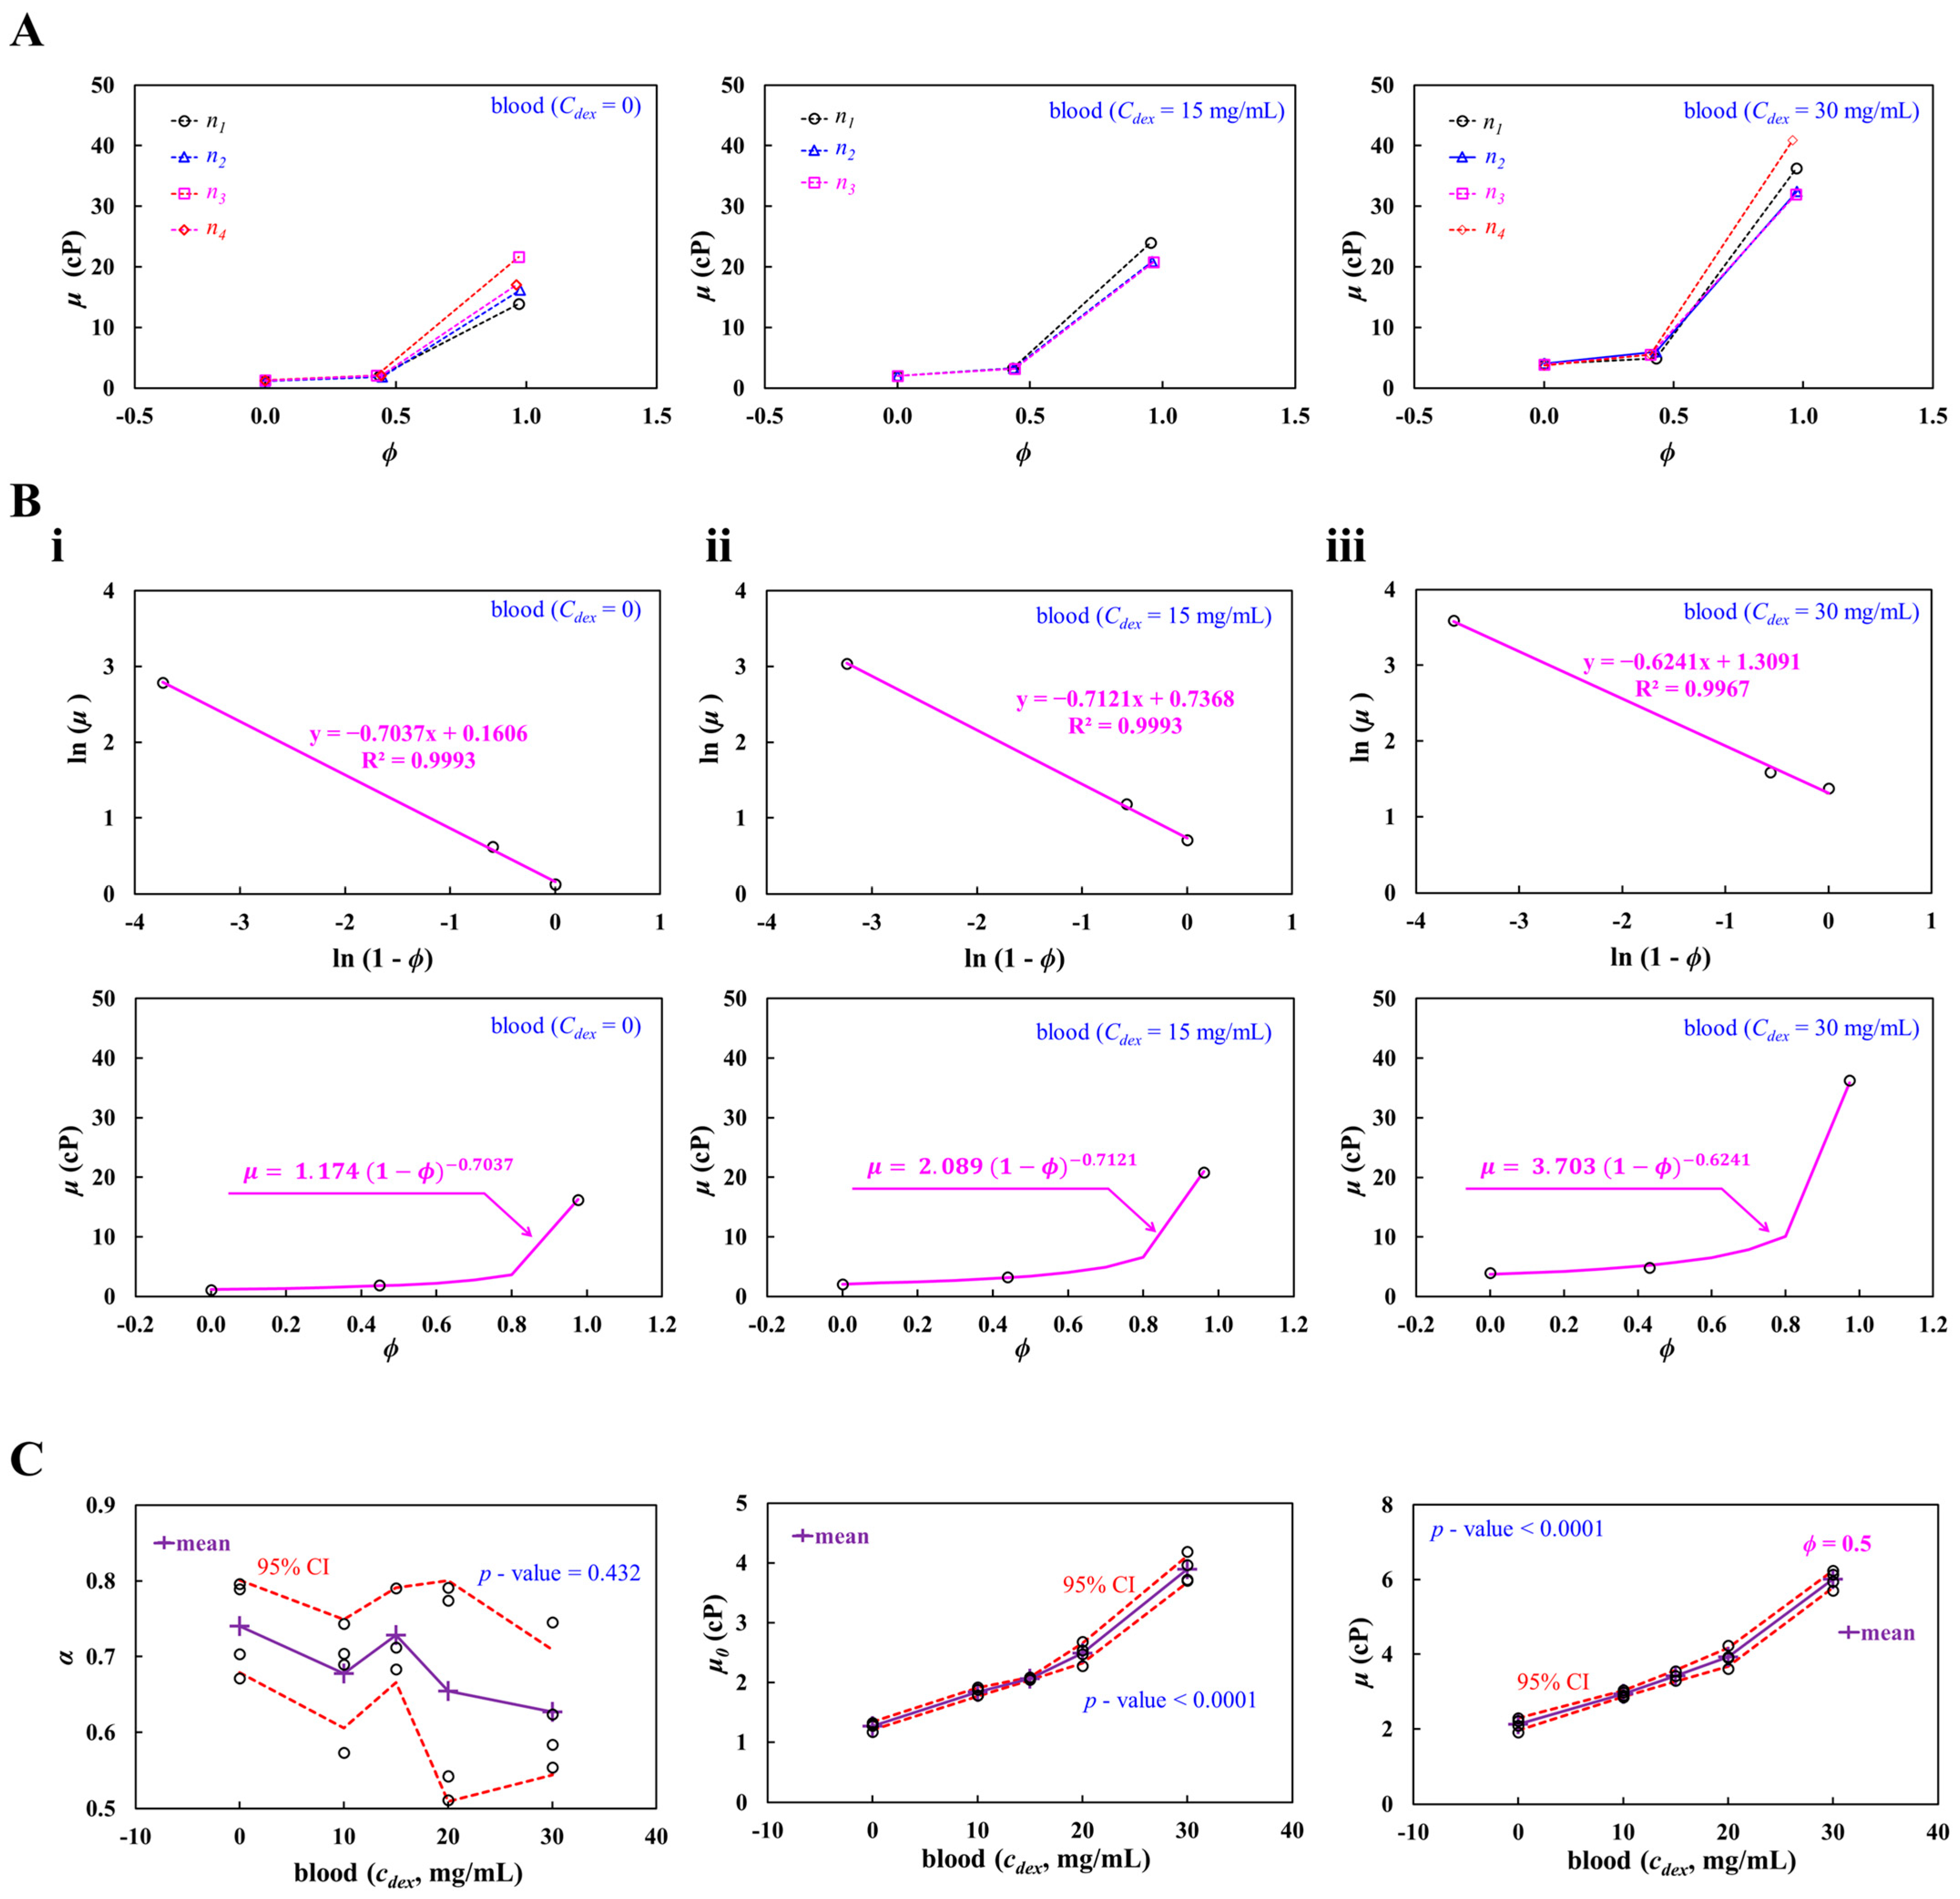
As shown in Figure 6A, three hematocrit–viscosity datasets are presented for Cdex = 0, 15, and 30 mg/mL. The left, middle, and right panels show the datasets for Cdex = 0, 15, and 30 mg/mL, respectively. The number of test blood samples was set to Sn = 3~4.
Figure 6.
Contribution of blood medium to the full hematocrit–viscosity curve. Herein, test blood was prepared by adding normal RBCs into a specific concentration of the dextran solution (Cdex = 5~30 mg/mL). Blood viscosity was obtained at a flow rate of 5 mL/h. (A) Three hematocrit–viscosity datasets with respect to Cdex = 0, 15, and 30 mg/mL. (B) Full hematocrit–viscosity curve identification with respect to Cdex. (i) Linear regression and full hematocrit–viscosity curve for blood (Cdex = 0). (ii) Linear regression and full hematocrit–viscosity curve for blood (Cdex = 15 mg/mL). (iii) Linear regression and full hematocrit–viscosity curve for blood (Cdex = 30 mg/mL). (C) Contribution of dextran solution to α, μ0, and μ (ϕ = 0.5). The left-side panel shows variations in α with respect to Cdex. The red-dashed line represents the 95% CI. According to statistical analysis (ANOVA-test), the p-value was obtained as 0.432. The mid-side panel depicts variations in μ0 with respect to Cdex. The ANOVA test gave a p-value < 0.0001. The right-side panel shows variations in μ (ϕ = 0.5) with respect to Cdex. The ANOVA test provided a p-value < 0.0001.
Using the hematocrit–viscosity datasets with respect to the test blood (Cdex), linear regression analysis was conducted to find out the coefficients of the K-D regression model (i.e., α, and μ0). The best-fitted curve and full hematocrit–viscosity curve were then represented with respect to Cdex = 0, 15, and 30 mg/mL. Figure 6(Bi) represents the linear regression and full hematocrit–viscosity curve for the test blood (Cdex = 0). Linear regression analysis gave the best-fitted curve as ln (μ) = −0.7037 ln (1 − ϕ) + 0.1606 (R2 = 0.9993); α and μ0 of the K-D model were identified as α = 0.7037 and μ0 = 1.174 cP. The full hematocrit–viscosity curve was then obtained as . Figure 6(Bii) depicts the linear regression and full hematocrit–viscosity curve for blood (Cdex = 15 mg/mL). Linear regression analysis gave the best-fitted curve as ln (μ) = −0.7121 ln (1 − ϕ) + 0.7368 (R2 = 0.9993). The full hematocrit–viscosity curve was then obtained as . Figure 6(Biii) shows the linear regression and full hematocrit–viscosity curve for blood (Cdex = 30 mg/mL). Linear regression analysis provided the best-fitted curve as ln (μ) = −0.6241 ln (1 − ϕ) + 1.3091 (R2 = 0.9967). The full hematocrit–viscosity curve was then obtained as .
Based on the full hematocrit–viscosity curve obtained from the three datasets, as shown in Figure 6C, variations in α, μ0, and μ (ϕ = 0.5) are represented as a function of Cdex. The left-side panel shows variations in α with respect to Cdex. The red-dashed line represents the 95% CI. The α tended to decrease slightly over Cdex. From the statistical test (i.e., ANOVA-test, p-value = 0.432), the dextran solution did not contribute to decreasing α significantly. The mid-side panel depicts variations in μ0 with respect to Cdex. According to the statistical test (i.e., ANOVA-test, p-value < 0.001), the dextran solution had a strong impact on μ0. Considering previous studies [60,61,62], it was confirmed that the dextran solution contributed to increasing μ0 significantly. Based on the full hematocrit–viscosity curve, blood viscosity was estimated at ϕ = 0: μ (ϕ = 0.5). The right-side panel shows variations in μ (ϕ = 0.5) with respect to Cdex. The results indicated that blood viscosity was increased significantly at higher concentrations of the dextran solution. The statistical test (i.e., ANOVA-test, p-value < 0.001) confirmed that the dextran solution had a strong impact on the viscosity of the suspended blood (ϕ = 0.5).
The experimental results show that the exponent (α) of the K–D model did not differ significantly with respect to the dextran concentration, whereas μ0 increased markedly as the dextran concentration increased. These findings suggest that the suspending medium had a strong effect on the μ0 of the K–D regression model.
3.5. Contribution of Rigidified RBCs to Full Hematocrit–Viscosity Curve
In the last subsection, to evaluate the contribution of rigidified RBCs to the full hematocrit–viscosity curve [63,64,65], normal RBCs were rigidified by incubating them into a GA solution, and 1× PBS was selected as the blood medium. Test blood (ϕvol = 0.5) was then prepared by adding GA-induced rigidified RBCs into 1× PBS. The blood viscosity of the test blood was measured at a flow rate of 5 mL/h.
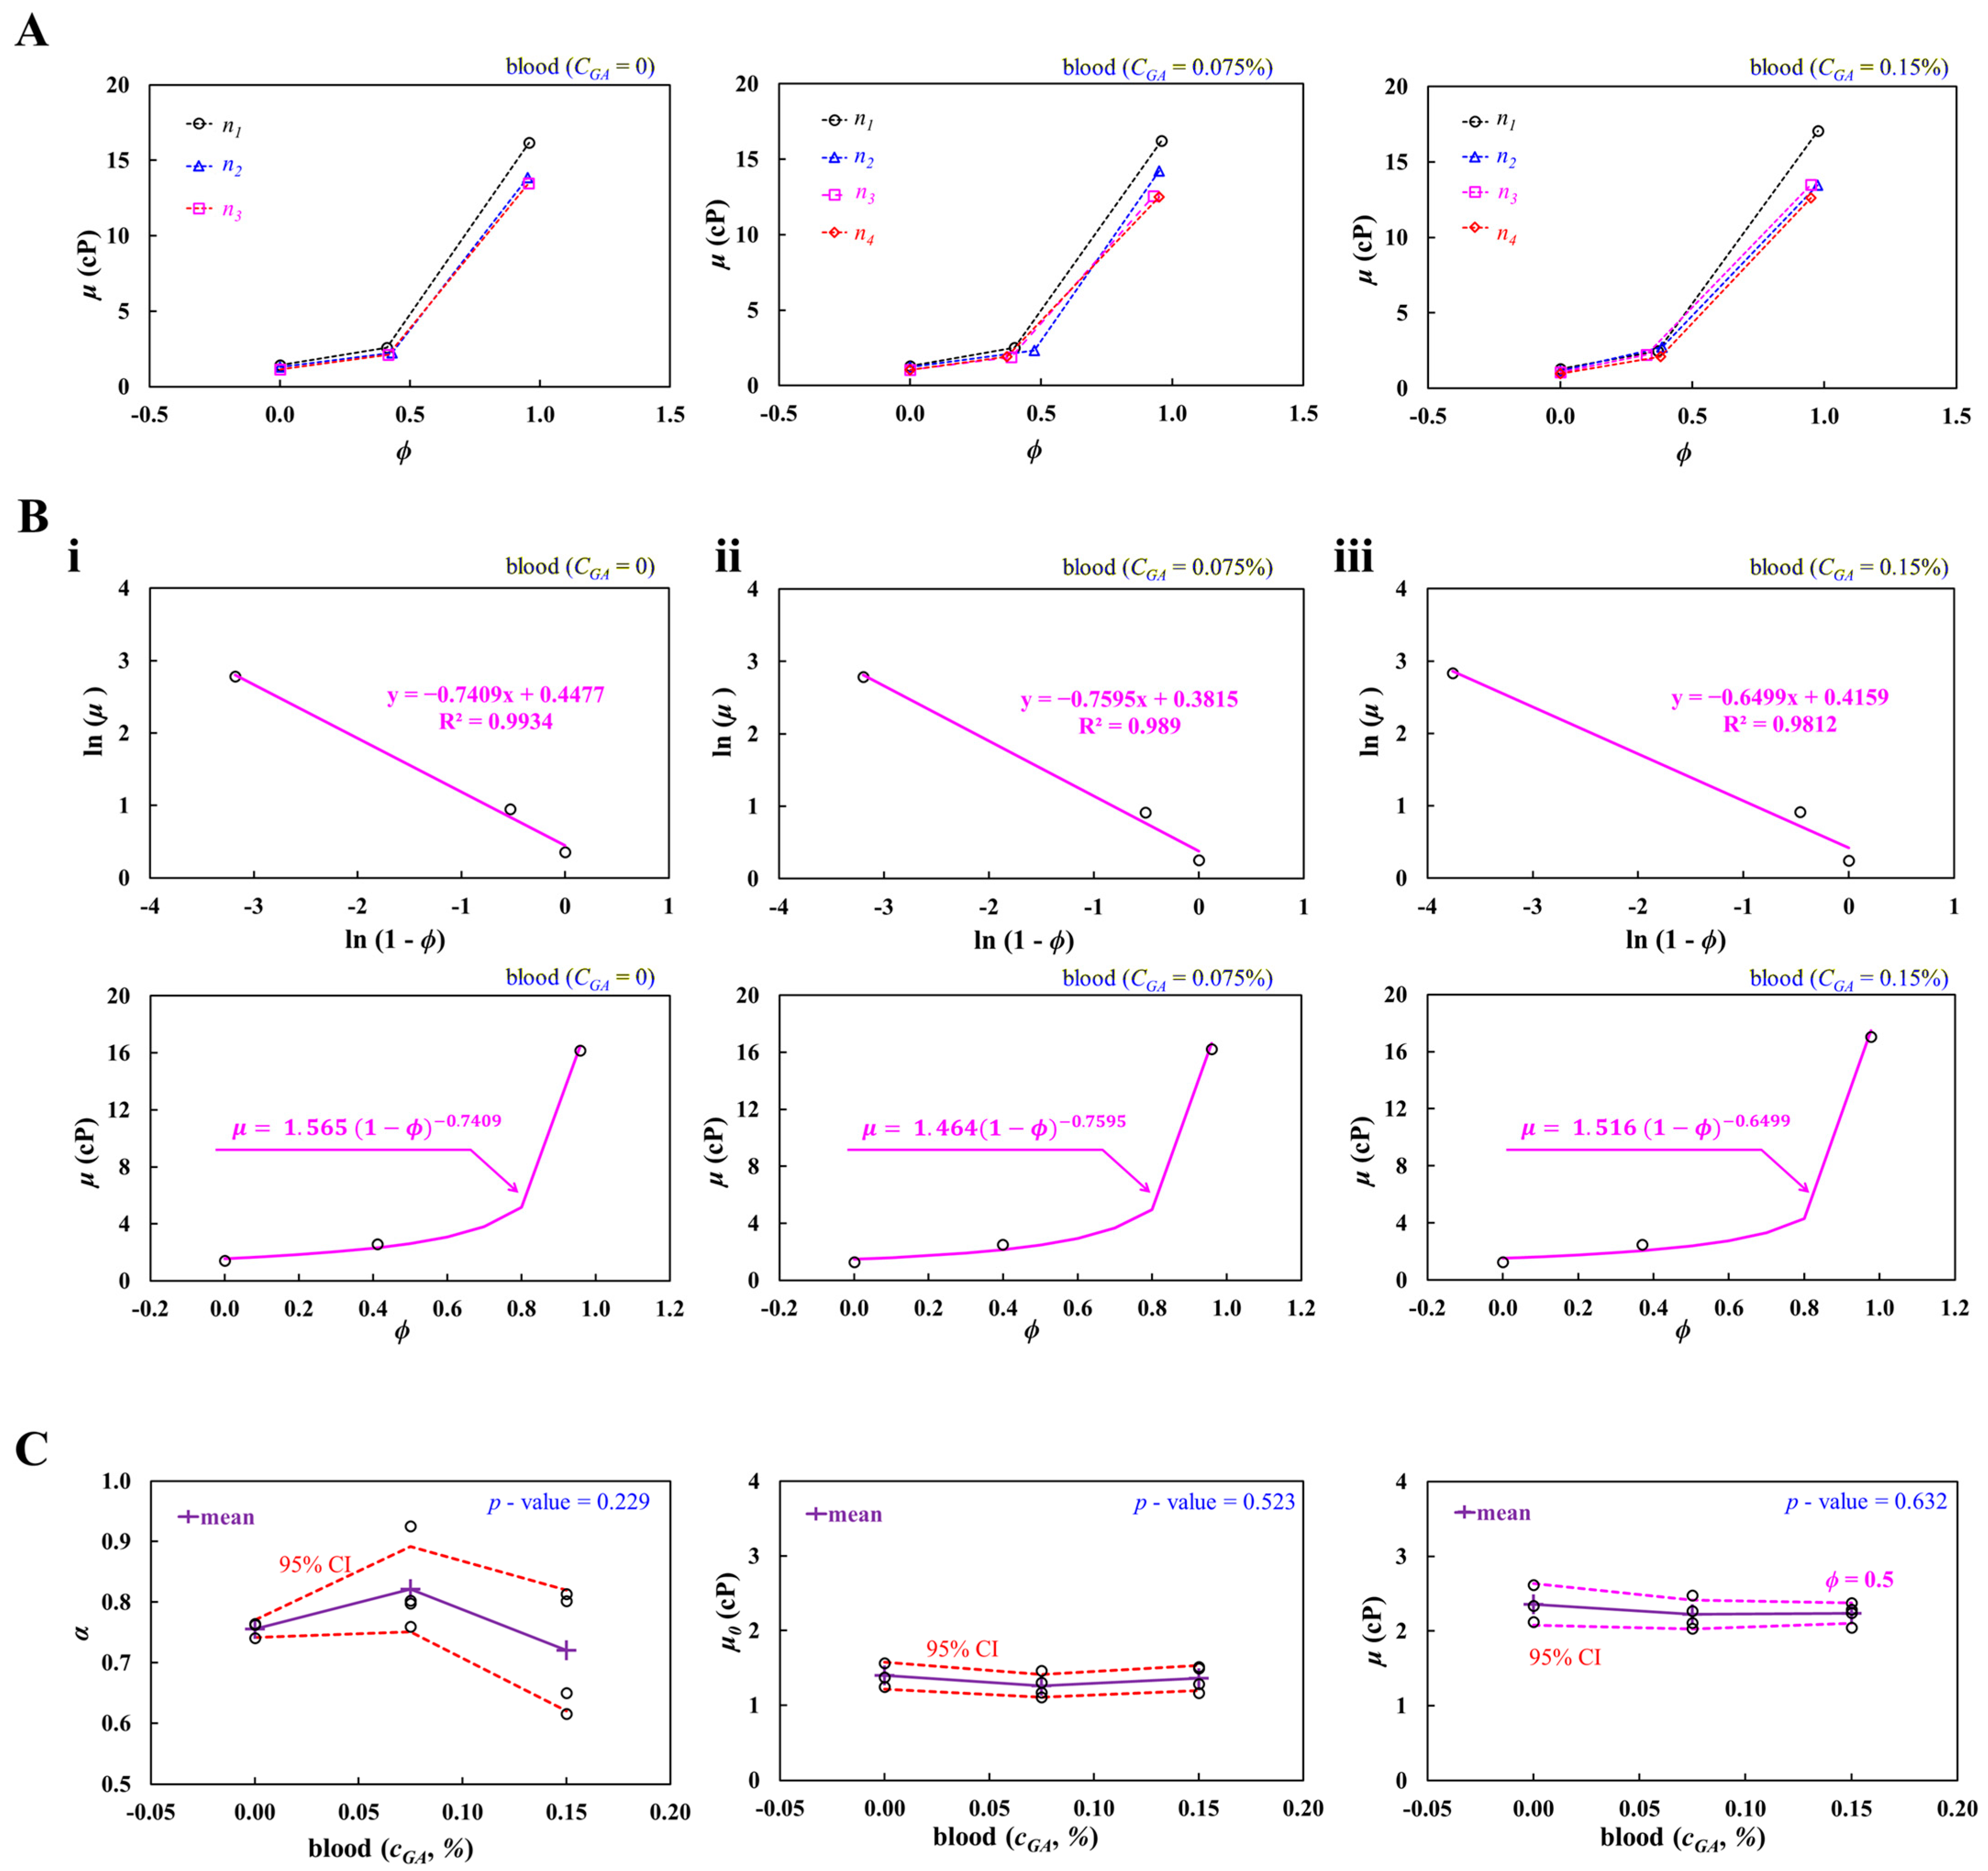
As shown in Figure 7A, with respect to GA concentration (CGA = 0, 0.075%, and 0.15%), three hematocrit–viscosity datasets are plotted on the ϕ-μ axes. Herein, the CGA denoted 1× PBS. The number of test blood was set to Sn = 3~4. The hematocrit of the test blood (ϕ) varied substantially, even though the RBC volume fraction was fixed at 0.5. After GA treatment, RBCs became rigid and tended to adhere to the tube and pipette walls after centrifugation, making it difficult to transfer a precisely defined cell volume. As a result, hematocrit variation increased in hardened blood samples, particularly at CGA = 0.075% and 0.15%, whereas the control blood showed consistent hematocrit values, confirming reproducibility of the measurement method itself. Based on three hematocrit–viscosity datasets, linear regression analysis was conducted to get the full hematocrit–viscosity curve with respect to CGA.
Figure 7.
Contribution of RBC deformability to the full hematocrit–viscosity curve. Herein, test blood was prepared by adding GA-induced rigidified RBCs into 1× PBS. The blood viscosity of the test blood was measured at a flow rate of 5 mL/h. (A) Three hematocrit–viscosity datasets with respect to GA concentration (CGA = 0, 0.075%, and 0.15%). (B) Full hematocrit–viscosity curve identification with respect to CGA. (i) Linear regression and full hematocrit–viscosity curve for blood (CGA = 0). (ii) Linear regression and full hematocrit–viscosity curve for blood (CGA = 0.075%). (iii) Linear regression and full hematocrit–viscosity curve for blood (CGA = 0.15%). (C) Contribution of GA-treated hardened RBCs to α, μ0, and μ (ϕ = 0.5). The left-side panel shows variations in α with respect to CGA. The statistical test (ANOVA-test) gave a p-value = 0.229. The mid-side panel depicts variations in μ0 with respect to CGA. The ANOVA-test provided a p-value = 0.523. The right-side panel shows variations of μ (ϕ = 0.5) with respect to CGA. The ANOVA test gave a p-value = 0.632.
Figure (7Bi) shows the linear regression analysis and full hematocrit–viscosity curve for the test blood (CGA = 0). According to the linear regression analysis, the best-fitted curve was obtained as ln (μ) = −0.7409 ln (1 − ϕ) + 0.4477 (R2 = 0.9934). Two coefficients (α, μ0) of the K-D model were obtained as α = 0.7409 and μ0 = 1.564 cP. The full hematocrit–viscosity curve was then obtained as . Figure 7(Bii) depicts the linear regression analysis and full hematocrit–viscosity curve for blood (CGA = 0.075%). The linear regression analysis gave the best-fitted curve as ln (μ) = −0.7595 ln (1 − ϕ) + 0.3815 (R2 = 0.989). Two coefficients (α, μ0) of the K-D model were obtained as α = 0.7595 and μ0 = 1.464 cP. The full hematocrit–viscosity curve was then obtained as . Figure 7(Biii) exhibits the linear regression analysis and full hematocrit–viscosity curve for blood (CGA = 0.15%). The linear regression analysis gave the best-fitted curve as ln (μ) = −0.6499 ln (1 − ϕ) + 0.4159 (R2 = 0.9812). The full hematocrit–viscosity curve was then obtained as .
As shown in Figure 7C, variation in α, μ0, and μ (ϕ = 0.5) are plotted as a function of CGA. The left-side panel shows variations in α with respect to CGA. The red-dashed line represents the 95% CI. From the statistical test (i.e., ANOVA-test, p-value = 0.229), the GA-treated hardened RBCs did not contribute to decreasing α significantly. Specifically, the α decreased slightly between CGA = 0.075% and CGA = 0.15%. The mid-side panel depicts variations in μ0 with respect to CGA. According to the statistical test (i.e., ANOVA-test, p-value = 0.523), the GA-induced rigidified RBCs did not affect μ0 significantly. Furthermore, because 1× PBS was used as the suspending medium for the test blood, μ0 was confirmed to be independent of the GA solution concentration. The right-side panel shows variations in μ (ϕ = 0.5) with respect to CGA. The blood viscosity did not show a substantial difference with respect to CGA. The statistical test (i.e., ANOVA-test, p-value = 0.632) confirmed that the rigidified RBCs did not have a strong impact on the viscosity of suspended blood (ϕ = 0.5). According to the previous study [61], blood viscosity (ϕvol = 0.3) did not show a substantial difference up to CGA = 0.1%. On the other hand, RBC deformability decreases progressively with increasing GA concentration, including a nearly linear decline of up to 0.08% GA by ektacytometry and marked rigidification even at low GA levels such as 0.01~0.025% [66]. However, the present method did not exhibit a substantial difference in blood viscosity within 0.15% of the GA solution. Thus, it was inferred that the present results showed consistent trends with respect to CGA.
From the experimental results, the rigidified RBCs did not have a strong impact on the coefficients of the K-D regression model. Blood viscosity (ϕ = 0.5) remained constant up to CGA = 0.15%.
As a limitation of this study, the proposed method was validated only under limited experimental conditions, including specific flow rates, dextran concentrations, and GA concentrations. Because the experiments were conducted using in vitro test blood prepared with a dextran solution or GA-induced rigidified RBCs in 1× PBS, the results may not fully represent the rheological behavior of native whole blood under physiological conditions. Therefore, further studies with larger sample sizes and broader experimental conditions will be needed to validate the robustness and practical applicability of the proposed method. In addition, to measure blood viscosity resulting from RBC aggregation in a microfluidic environment, the flow rate should be set to less than 0.15 mL/h (i.e., shear rate < 100 s−1). However, as the current microfluidic system did not guarantee a consistent flow rate at the low shear rate, blood viscosity was measured at a sufficiently high shear rate. It will be necessary to improve the blood delivery system, which can maintain a low flow rate, and measure blood viscosity consistently.
4. Conclusions
This study demonstrated the feasibility of reconstructing the full hematocrit–viscosity curve from only three selected datasets using the K–D regression model. The results suggested that the full hematocrit–viscosity curve obtained from the three selected datasets was in good agreement with the experimental data and yielded a lower fitting error than the conventional method using all datasets. The exponent of the K–D model was strongly influenced by the midpoint hematocrit, whereas μ0 was mainly affected by the suspending medium. In contrast, GA-induced rigidified RBCs did not significantly affect μ0 within a 0.15% concentration. In conclusion, the proposed method provided a simple, efficient, and reliable approach for estimating the full hematocrit–viscosity curve.
Funding
This work was supported by the Basic Science Research Program through the NRF funded by the Ministry of Education (NRF-2021R1I1A3040338).
Institutional Review Board Statement
This study was performed in accordance with the Declaration of Helsinki and was approved by the Ethics Committee of Chosun University (reference code: 2-1041055-AB-N-01-2021-80).
Informed Consent Statement
Not applicable.
Data Availability Statement
The original contributions presented in this study are included in the article material. Further inquiries can be directed to the corresponding author.
Acknowledgments
During the preparation of this manuscript, the author used ChatGPT (Version 5.4) for the purposes of generating text. The author has reviewed and edited the output and takes full responsibility for the content of this publication.
Conflicts of Interest
The author declares no conflicts of interest.
References
- Baskurt, O.K.; Meiselman, H.J. Blood rheology and hemodynamics. Semin. Thromb. Hemost. 2003, 29, 435–450. [Google Scholar] [CrossRef] [Scilit]
- Sitina, M.; Stark, H.; Schuster, S. Optimal hematocrit theory: A review. J. Appl. Physiol. 2024, 137, 494–509. [Google Scholar] [CrossRef] [Scilit]
- Subendran, S.; Wang, Y.C.; Lu, Y.H.; Chen, C.Y. The evaluation of zebrafish cardiovascular and behavioral functions through microfluidics. Sci. Rep. 2021, 11, 13801. [Google Scholar] [CrossRef] [Scilit]
- Peters, S.A.; Woodward, M.; Rumley, A.; Tunstall-Pedoe, H.D.; Lowe, G.D. Plasma and blood viscosity in the prediction of cardiovascular disease and mortality in the Scottish Heart Health Extended Cohort Study. Eur. J. Prev. Cardiol. 2017, 24, 161–167. [Google Scholar] [CrossRef] [Scilit]
- Deng, Y.; Papageorgiou, D.P.; Li, X.; Perakakis, N.; Mantzoros, C.S.; Dao, M.; Karniadakis, G.E. Quantifying fibrinogen-dependent aggregation of red blood cells in type 2 diabetes mellitus. Biophys. J. 2020, 119, 900–912. [Google Scholar] [CrossRef] [Scilit]
- Cho, Y.I.; Mooney, M.P.; Cho, D.J. Hemrheological disorders in diabetes mellitus. J. Diabetes Sci. Technol. 2008, 2, 1130–1138. [Google Scholar] [CrossRef] [Scilit]
- Waltz, X.; Hardy-Dessources, M.D.; Lemonne, N.; Mougenel, D.; Lalanne-Mistrih, M.L.; Lamarre, Y.; Tarer, V.; Tressieres, B.; Etienne-Julan, M.; Hue, O.; et al. Is there a relationship between the hematocrit-to-viscosity ratio and microvascular oxygenation in brain and muscle? Clin. Hemorheol. Microcirc. 2015, 59, 37–43. [Google Scholar] [CrossRef] [Scilit]
- Mehri, R.; Mavriplis, C.; Fenech, M. Red blood cell aggregates and their effect on non-Newtonian blood viscosity at low hematocrit in a two-fluid low shear rate microfluidic system. PLoS ONE 2018, 13, e0199911. [Google Scholar] [CrossRef] [Scilit]
- Kim, B.J.; Lee, Y.S.; Zhbanov, A.; Yang, S. A physiometer for simultaneous measurement of whole blood viscosity and its determinants: Hematocrit and red blood cell deformability. Analyst 2019, 144, 3144–3157. [Google Scholar] [CrossRef] [Scilit]
- Trejo-Soto, C.; Hernandez-Machado, A. Normalization of blood viscosity according to the hematocrit and the shear rate. Micromachines 2022, 13, 357. [Google Scholar] [CrossRef] [Scilit]
- Li, G.; Ye, T.; Yang, B.; Wang, S.; Li, X. Temporal-spatial heterogeneity of hematocrit in microvascular networks. Phys. Fluids 2023, 35, 021906. [Google Scholar] [CrossRef] [Scilit]
- Riera-Llobet, C.; Méndez-Mora, L.; Cabello-Fusarés, M.; Hernández-Machado, A. Altered blood rheology in multiwidth microchannels: Hematocrit and tonicity variation. Phys. Fluids 2023, 35, 082017. [Google Scholar] [CrossRef] [Scilit]
- Zhao, H.; Han, H.; Lin, Q.; Huang, L.; Su, X.; Fang, Y.; Zhang, Y.; Su, E.; Chen, Z.; Li, S.; et al. A new hematocrit measurement method using a chemiluminescence biosensor and its application in a chemiluminescence immunoassay platform for myocardial markers detection with whole blood samples. Biosensors 2023, 13, 3. [Google Scholar] [CrossRef] [Scilit]
- Zucchini, L.; Ajcevic, M.; Coda Zabetta, C.D.; Greco, C.; Fernetti, C.; Moretto, C.; Pennini, S.; Accardo, A. Characterization of a novel approach for neonatal hematocrit screening based on penetration velocity in lateral flow test strip. Sensors 2023, 23, 2813. [Google Scholar] [CrossRef] [Scilit]
- Lee, C.A.; Paeng, D.G. Spatiotemporal blood viscosity by local hematocrit under pulsatile flow: Whole blood experiments and computational analysis. Comput. Biol. Med. 2025, 198, 111253. [Google Scholar] [CrossRef] [Scilit]
- Illibauer, J.; Clodi-Seitz, T.; Zoufaly, A.; Aberle, J.H.; Weninger, W.J.; Foedinger, M.; Elsayad, K. Diagnostic potential of blood plasma longitudinal viscosity measured using Brillouin light scattering. Proc. Natl. Acad. Sci. USA 2024, 121, e2323016121. [Google Scholar] [CrossRef] [Scilit]
- Chen, W.; Xia, M.; Zhu, W.; Xu, Z.; Cai, B.; Shen, H. A bio-fabricated tesla valves and ultrasound waves-powered blood plasma viscometer. Front. Bioeng. Biotechnol. 2024, 12, 1394373. [Google Scholar] [CrossRef] [Scilit]
- Bakhtiaridoost, S.; Musuroi, C.; Volmer, M.; Florescu, M. Optoelectronic microfluidic device for point-of-care blood plasma viscosity measurement. Lab Chip 2024, 24, 3305–3314. [Google Scholar] [CrossRef] [Scilit]
- Gautam, N.; Ram, R.; Bishnoi, V.; Sarkar, A. A low-cost and disposable capillary-based paper sensor for measuring blood-plasma viscosity using a smartphone app. Microfluid. Nanofluidics 2023, 27, 41. [Google Scholar] [CrossRef]
- Kang, H.; Jang, I.; Song, S.; Bae, S.C. Development of a paper-based viscometer for blood plasma using colorimetric analysis. Anal. Chem. 2019, 91, 4868–4875. [Google Scholar] [CrossRef] [Scilit]
- Lee, K.; Kinnunen, M.; Khokhlova, M.D.; Lyubin, E.V.; Priezzhev, A.V.; Meglinski, I.; Fedyanin, A.A. Optical tweezers study of red blood cell aggregation and disaggregation in plasma and protein solutions. J. Biomed. Opt. 2016, 21, 35001. [Google Scholar] [CrossRef] [Scilit]
- Kang, Y.J. Assessment of continuous flow-dependent red cell aggregation using a microfluidic chip. Appl. Sci. 2025, 15, 11481. [Google Scholar] [CrossRef] [Scilit]
- Charansonney, O.L.; Meseguer, E.; Goube, P.; Vicaut, E. Erythrocyte aggregation kinetics for studying the vascular phase of inflammation in patients with suspected acute coronary syndrome or acute stroke. Sci. Rep. 2025, 15, 38049. [Google Scholar] [CrossRef] [Scilit]
- Alexandrova-Watanabe, A.; Abadjieva, E.; Ivanova, M.; Gartcheva, L.; Langari, A.; Guenova, M.; Tiankov, T.; Nikolova, E.V.; Krumova, S.; Todinova, S. Quantitative assessment of red blood cell disaggregation in chronic lymphocytic leukemia via software image flow analysis. Fluids 2025, 10, 167. [Google Scholar] [CrossRef] [Scilit]
- Lee, C.A.; Farooqi, H.M.U.; Paeng, D.G. Axial shear rate: A hemorheological factor for erythrocyte aggregation under Womersley flow in an elastic vessel based on numerical simulation. Comput. Biol. Med. 2023, 157, 106767. [Google Scholar] [CrossRef] [Scilit]
- Weber-Fishkin, S.; Seidner, H.S.; Gunter, G.; Frame, M.D. Erythrocyte aggregation in sudden flow arrest is linked to hyperthermia, hypoxemia, and band 3 availability. J. Thromb. Haemost. 2022, 20, 2284–2292. [Google Scholar] [CrossRef] [Scilit]
- Maung Ye, S.S.; Kim, S. A mechanistic model of cross-bridge migration in RBC aggregation and disaggregation. Front. Bioeng. Biotechnol. 2022, 10, 1049878. [Google Scholar] [CrossRef] [Scilit]
- Charansonney, O.L.; Morel, P.; Dufaux, J.; Vicaut, E. Description and validation of a new, simple, easy-to handle, point-of-care technique for measuring erythrocyte aggregation kinetics. Sci. Rep. 2022, 12, 14798. [Google Scholar] [CrossRef] [Scilit]
- Lee, C.A.; Paeng, D.G. Numerical simulation of spatiotemporal red blood cell aggregation under sinusoidal pulsatile flow. Sci. Rep. 2021, 11, 9977. [Google Scholar] [CrossRef] [Scilit]
- Namgung, B.; Lee, T.; Tan, J.K.S.; Poh, D.K.H.; Park, S.; Chng, K.Z.; Agrawal, R.; Park, S.Y.; Leo, H.L.; Kim, S. Vibration motor-integrated low-cost, miniaturized system for rapid quantification of red blood cell aggregation. Lab Chip 2020, 20, 3930–3937. [Google Scholar] [CrossRef] [Scilit]
- You, J.; Park, C.-A.; Kim, A.-K.; Jeon, H.R.; Kim, D.-I.; Shin, S. Ultrasensitive microfluidic detection of red blood cell deformability: Age-related decline in deformability. Phys. Fluids 2025, 37, 081916. [Google Scholar] [CrossRef]
- Liu, W.; Xie, L.; Yang, J.; Gong, X.; Sun, D.; Zhang, C. A microfluidic device for detecting the deformability of red blood cells. Biosensors 2025, 15, 758. [Google Scholar] [CrossRef] [Scilit]
- Kajitani, K.; Ohtani, T.; Higuchi, R.; Chimura, M.; Sera, F.; Tsai, C.D.; Ueda, Y.; Nishimura, J.I.; Sakata, Y. An on-chip deformability checker demonstrates that the severity of iron deficiency is associated with increased deformability of red blood cells. Sci. Rep. 2025, 15, 19994. [Google Scholar] [CrossRef] [Scilit]
- Williams, D.C.; Wood, D.K. High-throughput quantification of red blood cell deformability and oxygen saturation to probe mechanisms of sickle cell disease. Proc. Natl. Acad. Sci. USA 2023, 120, e2313755120. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kang, Y.J.; Serhrouchni, S.; Makhro, A.; Bogdanova, A.; Lee, S.S. Simple assessment of red blood cell deformability using blood pressure in capillary channels for effective detection of subpopulations in red blood cells. ACS Omega 2022, 7, 38576–38588. [Google Scholar] [CrossRef] [Scilit]
- Matrai, A.A.; Varga, G.; Tanczos, B.; Barath, B.; Varga, A.; Horvath, L.; Bereczky, Z.; Deak, A.; Nemeth, N. In vitro effects of temperature on red blood cell deformability and membrane stability in human and various vertebrate species. Clin. Hemorheol. Microcirc. 2021, 78, 291–300. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Suzuki, T.; Takao, H.; Suzuki, T.; Fujimura, S.; Hataoka, S.; Kodama, T.; Aoki, K.; Ishibashi, T.; Yamamoto, M.; Yamamoto, H.; et al. Development of patient-specific apparent blood viscosity predictive models for computational fluid dynamics analysis of intracranial aneurysms with machine learning approaches. Comput. Methods Programs Biomed. 2025, 268, 108831. [Google Scholar] [CrossRef] [Scilit]
- Riva, A.; Sturla, F.; Caimi, A.; Pica, S.; Giese, D.; Milani, P.; Palladini, G.; Lombardi, M.; Redaelli, A.; Votta, E. 4D flow evaluation of blood non-Newtonian behavior in left ventricle flow analysis. J. Biomech. 2021, 119, 110308. [Google Scholar] [CrossRef] [Scilit]
- Pries, A.R.; Neuhaus, D.; Gaehtgens, P. Blood viscosity in tube flow: Dependence on diameter and hematocrit. Am. J. Physiol. 1992, 263, H1772–H1778. [Google Scholar] [CrossRef] [Scilit]
- Chien, S. Shear dependence of effective cell volume as a determinant of blood viscosity. Science 1970, 168, 977–979. [Google Scholar] [CrossRef] [Scilit]
- Noh, S.-M. Clinical significance of blood viscosity in patients with acute ischemic stroke. Sci. Rep. 2025, 15, 22424. [Google Scholar] [CrossRef] [Scilit]
- Mooney, M. The viscosity of a concentrated suspension of spherical particles. J. Colloid Sci. 1951, 6, 162–170. [Google Scholar] [CrossRef] [Scilit]
- Krieger, I.M.; Dougherty, T.J. A mechanism for non-Newtonian flow in suspensions of rigid spheres. Trans. Soc. Rheol. 1959, 3, 137–152. [Google Scholar] [CrossRef] [Scilit]
- Tao, R.; Huang, K. Reducing blood viscosity with magnetic fields. Phys. Rev. E 2011, 84, 001900. [Google Scholar] [CrossRef] [Scilit]
- Hund, S.; Kameneva, M.; Antaki, J. A quasi-mechanistic mathematical representation for blood viscosity. Fluids 2017, 2, 10. [Google Scholar] [CrossRef] [Scilit]
- Bull, B.S.; Fujimoto, K.; Houwen, B.; Klee, G.; van Hove, L.; van Assendelft, O.W. International council for standardization in haematology (ICSH) recommendations for surrogate reference method for the packed cell volume. Lab. Hematol. 2003, 9, 1–9. [Google Scholar]
- Pearson, T.C.; Guthrie, D.L. Trapped plasma in the microhematocrit. Am. J. Clin. Pathol. 1982, 78, 770–772. [Google Scholar] [CrossRef] [Scilit]
- Livshits, L.; Bilu, T.; Peretz, S.; Bogdanova, A.; Gassmann, M.; Eitam, H.; Koren, A.; Levin, C. Back to the gold standard: How precise is hematocrit detection today? Mediterr. J. Hematol. Infect. Dis. 2022, 14, e2022049. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Merlo, A.; Losserand, S.; Yaya, F.; Connes, P.; Faivre, M.; Lorthois, S.; Minetti, C.; Nader, E.; Podgorski, T.; Renoux, C.; et al. Influence of storage and buffer composition on the mechanical behavior of flowing red blood cells. Biophys. J. 2023, 122, 360–373. [Google Scholar] [CrossRef] [Scilit]
- Turner, T.; Hansen, A.; Kurach, J.; Acker, J.P. From development to implementation: Adjusting the hematocrit of deglycerolized red cell concentrates to meet regulatory standards. Transfus. Med. Hemother 2017, 44, 30–38. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oksuz, C.; Bicmen, C.; Tekin, H.C. Dynamic fluidic manipulation in microfluidic chips with dead-end channels through spinning: The Spinochip technology for hematocrit measurement, white blood cell counting and plasma separation. Lab Chip 2025, 25, 1926–1937. [Google Scholar] [CrossRef] [Scilit]
- Kang, Y.J. Quantitative monitoring of dynamic blood flows using coflowing laminar streams in a sensorless approach. Appl. Sci. 2021, 11, 7260. [Google Scholar] [CrossRef] [Scilit]
- O’Brien, S.; Kent, N.J.; Lucitt, M.; Ricco, A.J.; McAtamney, C.; Kenny, D.; Meade, G. Effective hydrodynamic shaping of sample streams in a microfluidic parallel-plate flow-assay device: Matching whole blood dynamic viscosity. IEEE Trans. Biomed. Eng. 2012, 59, 374–382. [Google Scholar] [CrossRef] [Scilit]
- Guillot, P.; Panizza, P.; Salmon, J.-B.; Joanicot, M.; Colin, A. Viscosimeter on a microfluidic chip. Langmuir 2006, 22, 6438–6445. [Google Scholar] [CrossRef] [Scilit]
- Kang, Y.J. Multiple-parameter sensing using an autonomous blood flow in a microfluidic chip. Results Eng. 2025, 28, 108413. [Google Scholar] [CrossRef] [Scilit]
- Kim, G.; Jeong, S.; Kang, Y.J. Ultrasound standing wave-based cell-to-liquid separation for measuring viscosity and aggregation of blood sample. Sensors 2020, 20, 2284. [Google Scholar] [CrossRef] [Scilit]
- Pirofsky, B. The determination of blood viscosity in man by a method based on Poiseuille’s law. J. Clin. Investig. 1953, 32, 292–298. [Google Scholar] [CrossRef] [Scilit]
- Rand, P.W.; Lacombe, E. Hemodilution, tonicity, and blood viscosity. J. Clin. Investig. 1964, 43, 2214–2226. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Flormann, D.; Schirra, K.; Podgorski, T.; Wagner, C. On the rheology of red blood cell suspensions with different amounts of dextran: Separating the effect of aggregation and increase in viscosity of the suspending phase. Rheol. Acta 2015, 55, 477–483. [Google Scholar] [CrossRef] [Scilit]
- Soutani, M.; Suzuki, Y.; Tateishi, N.; Maeda, N. Quantitative evaluation of flow dynamics of erythrocytes in microvessels: Influence of erythrocyte aggregation. Am. J. Physiol. 1995, 268, H1959–H1965. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kang, Y.J. Microfluidic chip for quantitatively assessing hemorheological parameters. Micromachines 2025, 16, 567. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bosek, M.; Ziomkowska, B.; Pyskir, J.; Wybranowski, T.; Pyskir, M.; Cyrankiewicz, M.; Napiorkowska, M.; Durmowicz, M.; Kruszewski, S. Relationship between red blood cell aggregation and dextran molecular mass. Sci. Rep. 2022, 12, 19751. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carr, R.; Cockelet, G.R. Rheology of suspensions of normal and hardened erythrocytes and their mixtures. J. Rheol. 1981, 25, 67–82. [Google Scholar] [CrossRef] [Scilit]
- Perazzo, A.; Peng, Z.; Young, Y.-N.; Feng, Z.; Wood, D.K.; Higgins, J.M.; Stone, H.A. The effect of rigid cells on blood viscosity: Linking rheology and sickle cell anemia. Soft Matter 2022, 18, 554–565. [Google Scholar] [CrossRef] [Scilit]
- Chien, S.; Usami, S.; Dellenback, R.J.; Gregersen, M.I. Blood viscosity: Influence of erythrocyte deformation. Science 1967, 157, 827–829. [Google Scholar] [CrossRef] [Scilit]
- Sosa, J.M.; Nielsen, N.D.; Vignes, S.M.; Chen, T.G.; Shevkoplyas, S.S. The relationship between red blood cell deformability metrics and perfusion of an artificial microvascular network. Clin. Hemorheol. Microcirc. 2014, 57, 275–289. [Google Scholar] [CrossRef] [Scilit]
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the author. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.