


Abstract
Background: Anterior disc displacement without reduction (ADDwoR) of the temporomandibular joint (TMJ) often leads to persistent pain and reduced quality of life (QoL). Conservative treatments frequently fail to provide adequate symptom relief. Objective: To assess the short-term (≥6 months) effectiveness of functional arthroplasty in reducing pain and improving QoL in patients with ADDwoR unresponsive to conservative therapies. Methods: A retrospective cohort study was conducted on 105 patients (median age 38 years, 80% female) treated at Santa Maria Hospital from January 2018 to December 2021. All patients had unilateral painful ADDwoR confirmed via MRI and underwent functional arthroplasty. Primary outcomes included pain reduction (VAS) and QoL improvements (QoL-TMJ questionnaire). Covariates such as age, gender, and baseline mood disturbances were analyzed for associations with surgical outcomes. Statistical analyses included the Wilcoxon rank test, Friedman’s ANOVA, and Spearman’s rank correlation. Results: Postoperative VAS scores significantly decreased (8.0 pre-op vs. 2.0 post-op, p < 0.001). QoL-TMJ scores improved significantly in pain (p < 0.001), activity (p < 0.05), mood (p < 0.001), and anxiety (p < 0.01), but no significant changes were observed in chewing and speaking functions. Improvements in QoL correlated strongly with pain reduction. Gender and age did not influence the outcomes, though females reported higher baseline mood disturbances. Conclusions: Functional arthroplasty effectively reduces pain and improves QoL in patients with ADDwoR, regardless of age or gender. However, limited improvement in chewing and speaking abilities highlights the need for targeted interventions. Future studies should assess the long-term outcomes to confirm the sustained benefits of this procedure.
1. Introduction
Temporomandibular joint disorders (TMDs) are one of the challenging pathologies to treat, with a higher prevalence in the female population, mainly in the fifth decade [1,2]. The most frequent symptoms of TMJ disorders are TMJ pain, headache, pain in the temporal and masseteric region, neck pain, tinnitus, vertigo, and limited jaw movements, particularly during chewing [3,4]. The etiology of TMDs includes trauma, parafunctional habits (such as bruxism and clenching), joint overloading, arthritides, psychological factors, and the ergonomic positioning of the head. The impact of psychological factors is difficult to calculate, but approximately 10% to 20% of patients with TMDs also manifest some form of anxiety (Axis II) [5]. Given the wide range of TMD symptoms and the difficulty in attributing a specific cause, TMDs are best understood as an interplay between joint pathology and psychological factors [6]. In the literature, different authors use different criteria to describe TMDs, so the reported prevalence of TMDs varies considerably. Among the adult population, the prevalence of signs and symptoms of TMDs is reported to be as high as 3% to 34% [7]. The main symptom of TMDs is TMJ pain, which could be associated with mechanical TMJ pathology, such as an inflammatory discal or retrodiscal status caused by disc displacement. Anterior displacement of the articular disc is the most common joint disorder [8]; the disc can be displaced even in other directions [9,10,11,12]. It can be reduced (ADDwR) or non-reduced (ADDwoR) with jaw opening. In the case of symptoms suggestive of ADDwoR, the most important radiological exam is MRI of the temporomandibular joint with a closed and open mouth [9,10,11,12]. Treatment modalities available for TMDs can be broadly classified into non-surgical, minimally invasive surgical, and open surgical procedures. The non-surgical treatment approaches include rest, counseling, and education of the patient [13], bite splints [14], physical therapy, and the regular use of non-steroidal anti-inflammatory medication (NSAIDs) [15] or injection of steroids [16] or botulinum toxin [17]. The minimally invasive surgical treatments include arthrocentesis and arthroscopy. Both these techniques involve the lavage of the superior compartment of the TMJ. Arthroscopy also involves the lysis of adhesions that may occur in the upper joint space and disc repositioning and fixation.
Patients who do not respond to the previously described techniques could be considered for surgical treatment. In the literature, different surgical techniques are described: discectomy [18,19], condylotomy [20], disc plication [21,22], disc repositioning [23], total joint prothesis [24], and functional arthroplasty [25]. The authors perform functional arthroplasty as a surgical technique for anterior disc displacement without reduction (ADDwoR) with persistent pain during jaw movement (jaw opening, chewing, lateral movements) and limited mouth opening (<40 mm) that has not responded to non-surgical and minimally invasive procedures. If left untreated, the articular disc may deform, degenerate, and progress to a more severe anterior displacement. Additionally, persistence of the internal derangement might produce condylar resorption with deformation and an overall decrease in condylar height [26]. The aim of this retrospective study is to evaluate quality of life and pain in patients with unilateral pain and ADDwoR unresponsive to non-surgical or minimally invasive techniques before and six months after functional arthroplasty using the VAS for pain assessment and a QoL-TMJ questionnaire. The QoL-TMJ questionnaire further investigates the patient’s pain, the main aspects of jaw functionality (such as chewing and speaking), the main aspects of daily living (such as general activities and recreational activities), and the main psychological elements that can be affected by TMJ disorders (such as mood and anxiety).
2. Materials and Methods
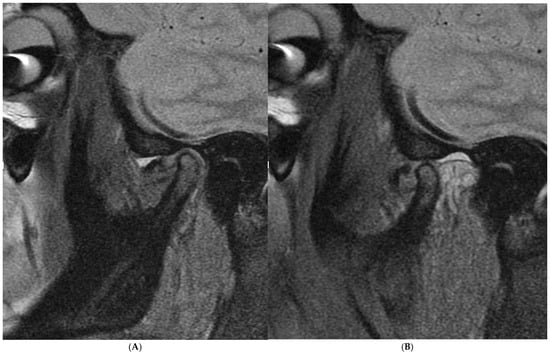
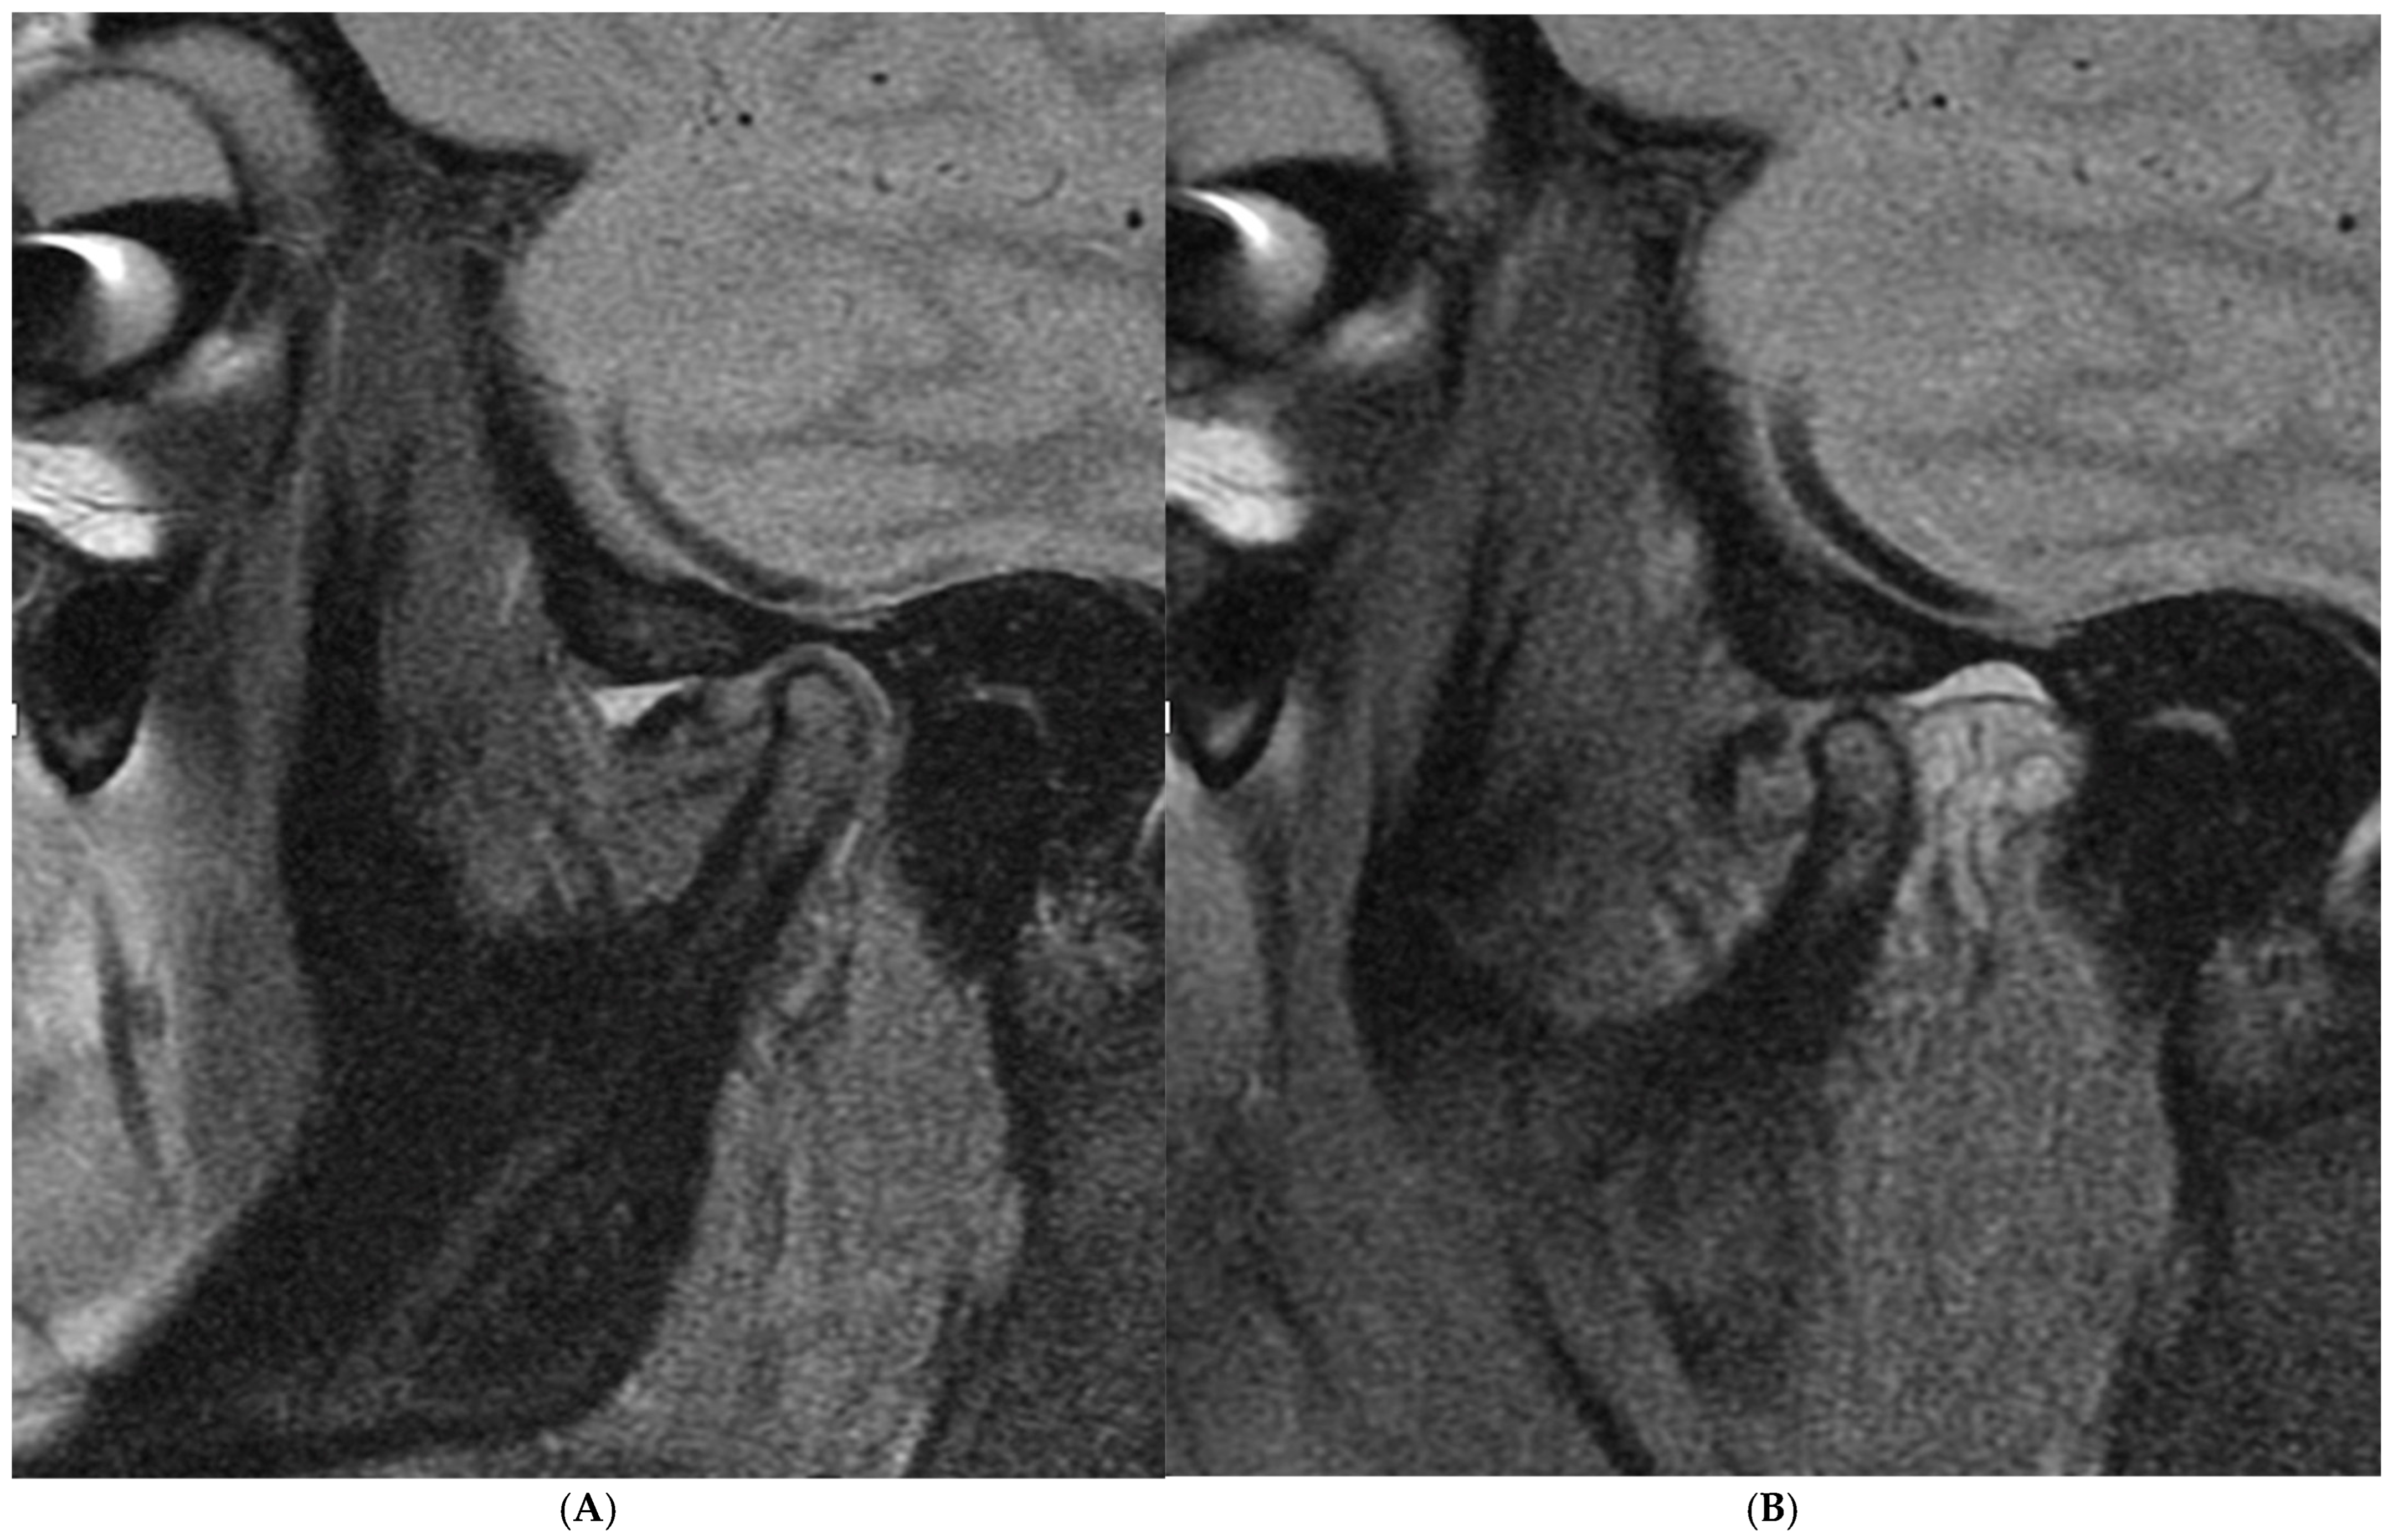
From January 2018 to December 2021, 203 patients with TMJ pain and limited jaw opening were admitted to Santa Maria Hospital in Terni with ADDwoR (anterior disc displacement without reduction). The diagnosis was confirmed by a 1.5 Tesla MRI, evaluating sagittal fat-suppressed T2W (FS-T2W) sequences with an open and closed mouth, in accordance with the diagnostic criteria (DC/TMD) [8,27] (Figure 1) and a clinical and radiological Wilkes classification [8,28].
Figure 1.
The picture shows an anterior disc dislocation with the mouth closed (A) and open (B) in MRI.
The radiological diagnosis of DDWoR was confirmed not only by the radiologist but also by two surgeons (F.S. and V.V.), who analyzed the DICOMs using the Horos DICOM viewer v.4.0.0. Horos is a free and open-source code software (FOSS) program that is distributed free of charge under the LGPL license at Horosproject.org and sponsored by Nimble Co LLC d/b/a Purview in Annapolis, MD, USA.
All patients underwent functional arthroplasty surgery performed by the same surgical team.
The inclusion criteria were as follows:
- -
- No previous diagnosis of other TMJ pathologies (trauma, rheumatologic and systemic diseases etc.);
- -
- A diagnosis of unilateral ADDWoR, (according to the diagnostic criteria (DC/TMD) and Wilkes classification);
- -
- A maximum assisted opening movement (MMO) < 40 mm;
- -
- A record of the TMJ VAS score for pain assessment and the QOL TMJ questionnaire results before and at least six months after surgical treatment;
- -
- Non-responsiveness to other non-invasive or minimally invasive techniques.
Out of the 203 patients admitted, 105 (51.7%) were included in the study, while 98 of them were not included (48.3%).
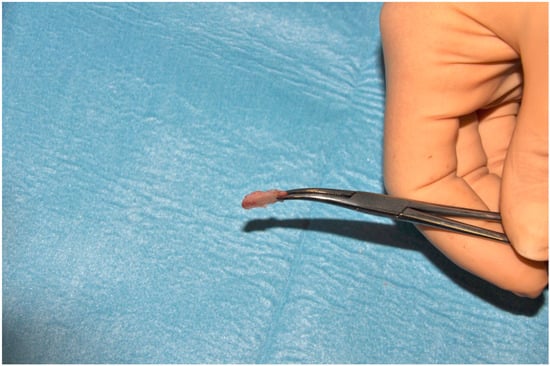
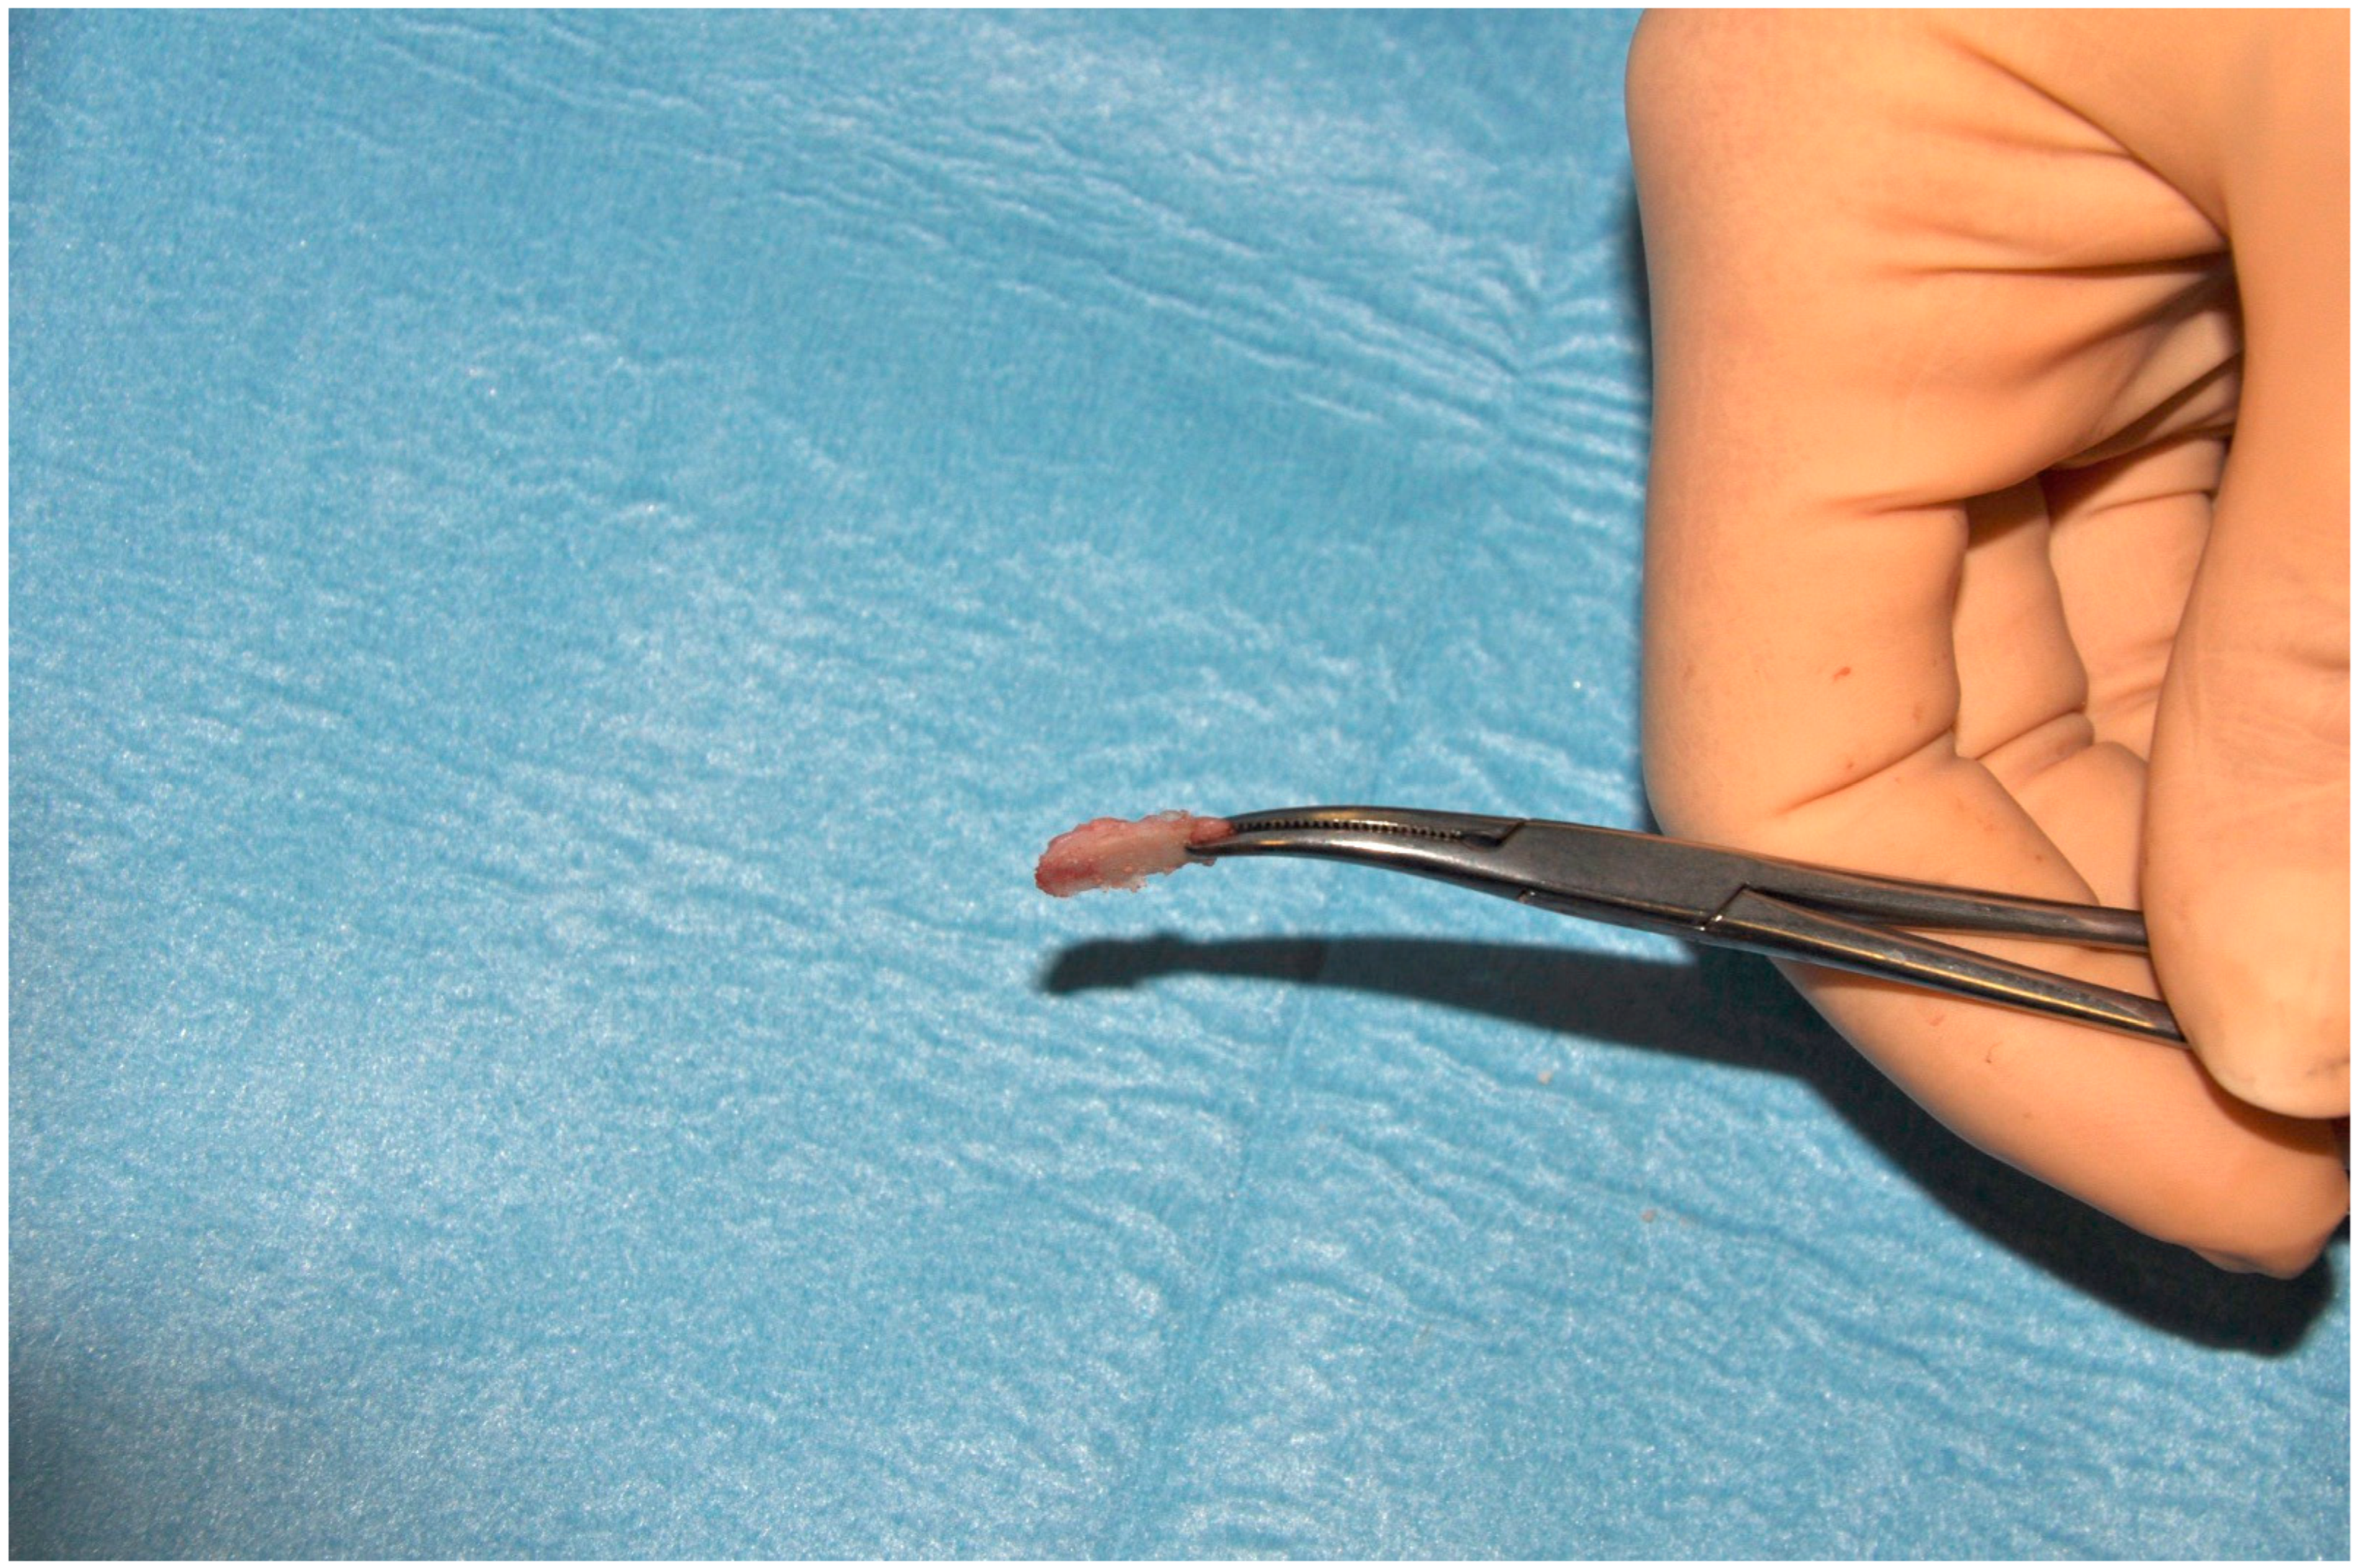
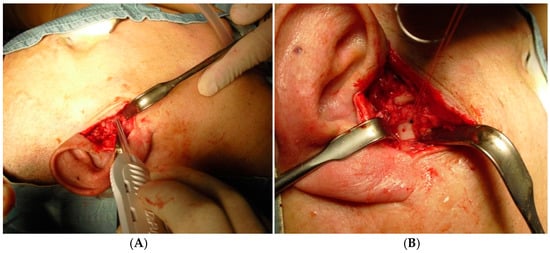
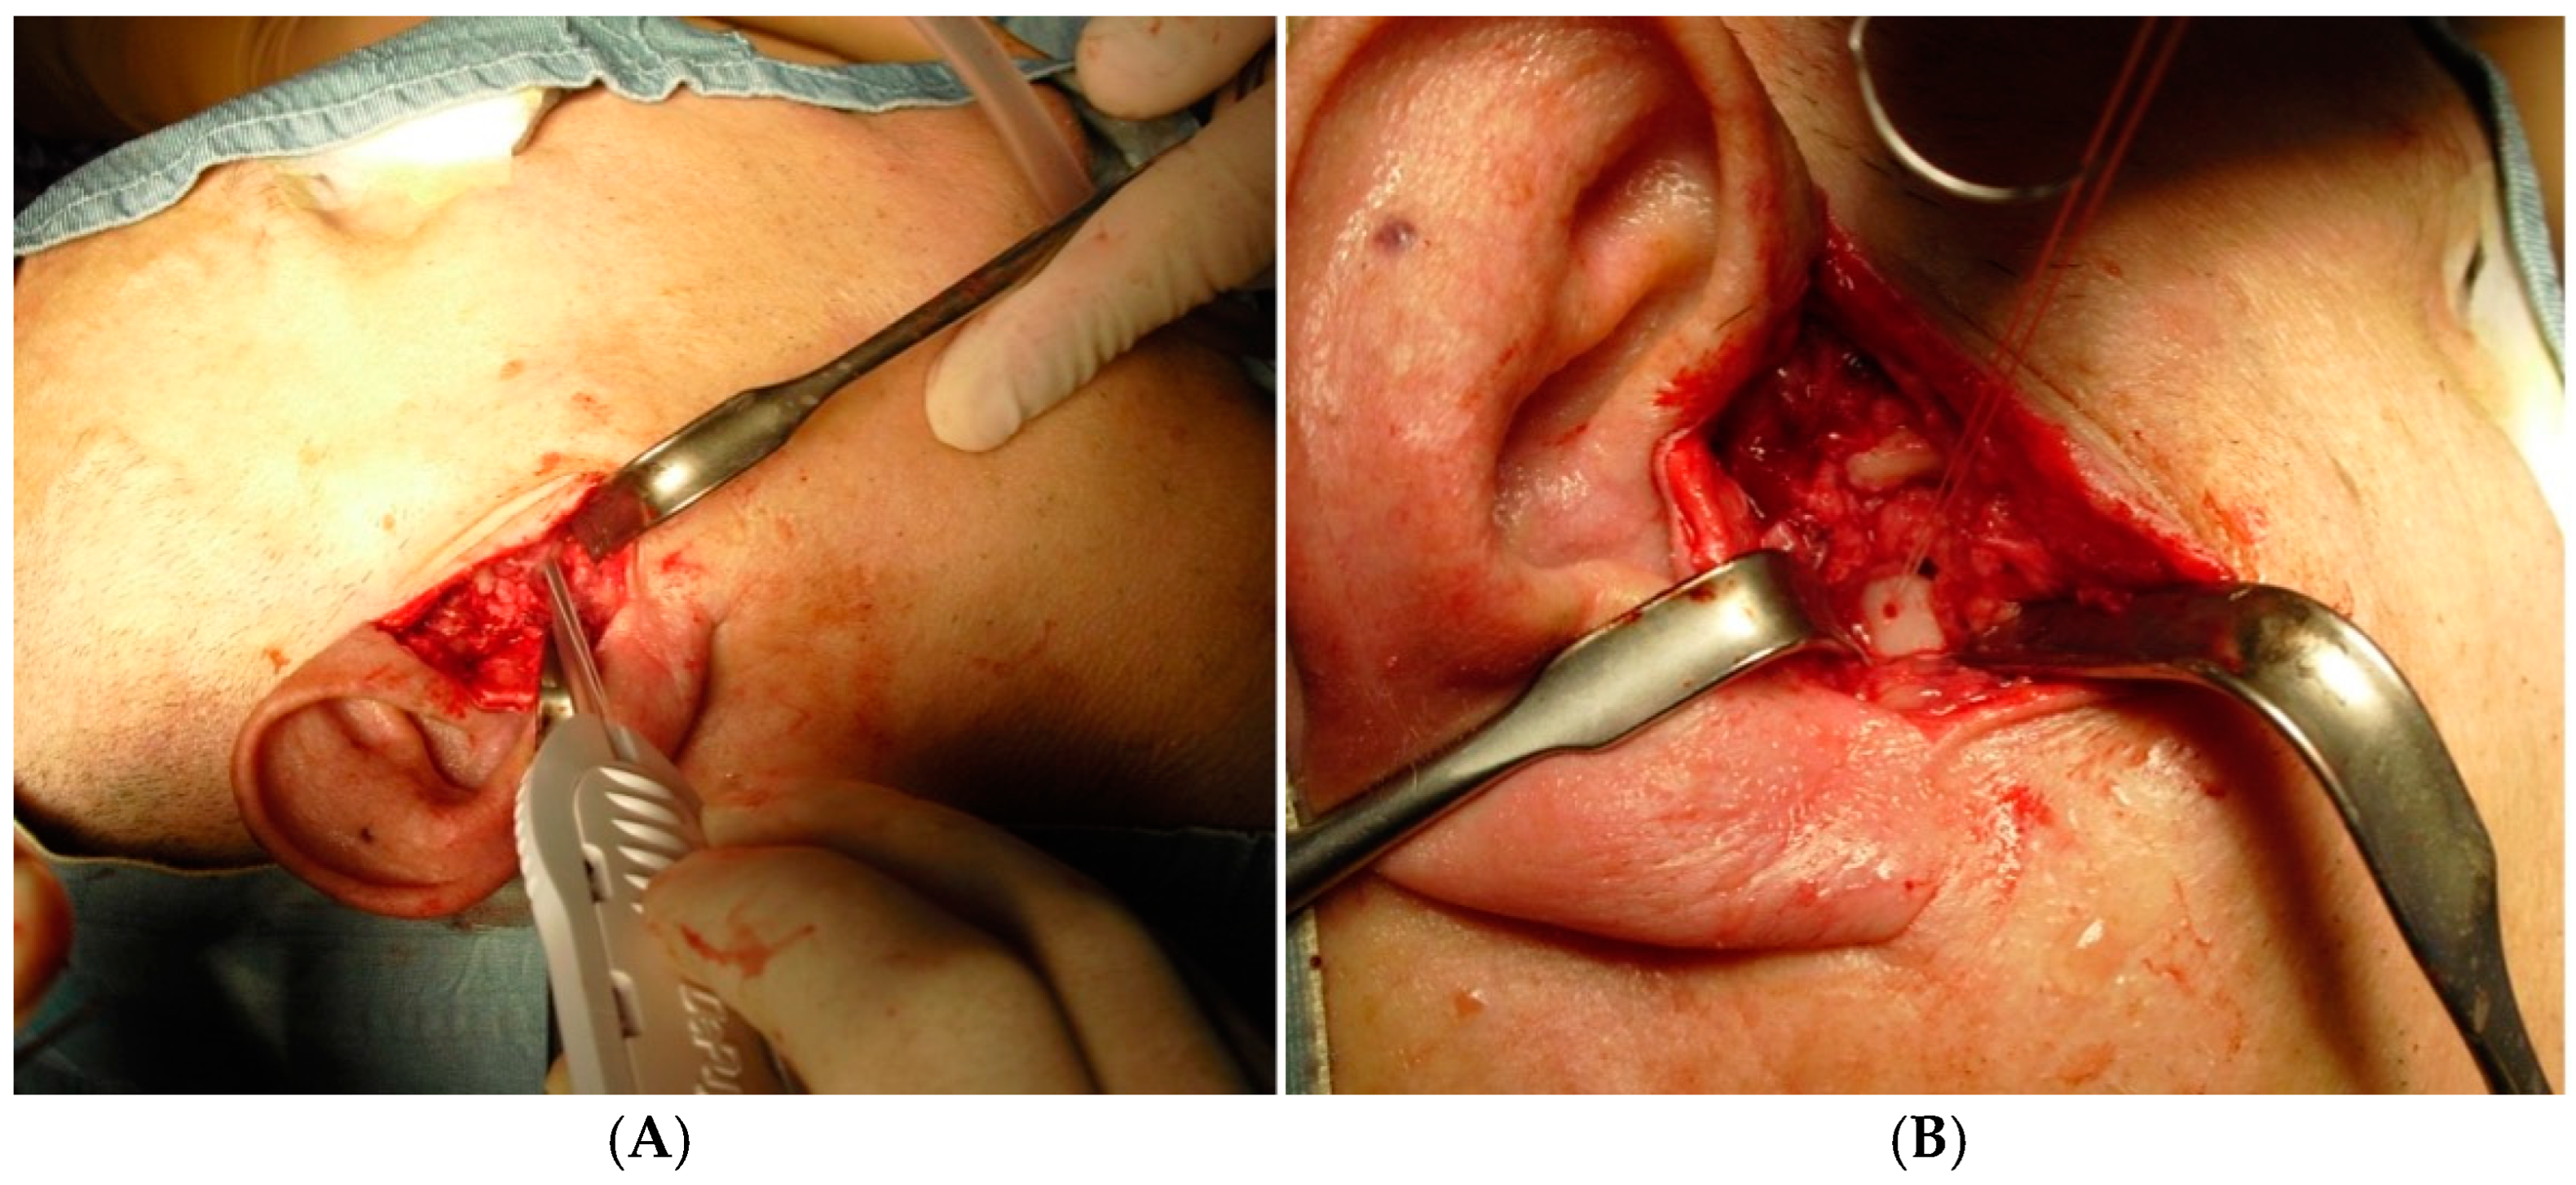
All patients underwent the same surgical procedure through an RHITNI (root of helix inter tragus notch incision), condylar head shaving (Figure 2), and disc repositioning with absorbable Mitek Microfix QuickAnchor Plus 1.3 (Figure 3), performed by the same surgeons (F.S and V.V.) [29,30,31,32].
Figure 2.
The picture shows the top of the condylar head, which has been removed for condylar remodeling. Condylar remodeling is performed using piezosurgery.
Figure 3.
The pictures show the positioning of the Mitek Microfix QuickAnchor, which is sutured to the disc in order to restore its original position at the head of the condyle (A,B).
The authors collected data from the hospital’s medical records. These data included the following: gender, age, nationality, medical comorbidities, symptoms, the visual analogic scale (VAS) score for TMJ pain assessment, the quality-of-life TMJ questionnaire (QoL-TMJ) before and six months after surgery, clinical signs, and radiological exams. The VAS assesses the patient’s TMJ pain on a scale from 0 to 10, where 0 indicates no pain and 10 represents the worst possible pain.
The TMJ-QoL, first proposed by Dimitroulis in 2010 [2], was based on the University of Washington QoL questionnaire for patients with head and neck oncology [33]. It was then adapted to patients with TMJ who were undergoing joint surgery and has previously been validated as an effective tool for evaluating the patient experience in relation to their TMJ-related quality of life post-surgery (Table 1) [2,34,35].
Table 1.
TMJ qualify of life (TMJ-QoL) questionnaire.
The first question (A) is about TMJ pain and the possible pain treatment with both NSAIDs and stronger analgesics like opioids. The following six questions (B to G) are about how the TMJ affects the patient’s daily activities, either involving the joint directly (chewing, talking) or indirectly (recreational and normal activities, and the feeling of bad mood and anxiety). The eighth question (H) investigates what part of the patient’s life was affected by the TMJ pain the month before surgery (the patient can circle up to three answers, which refer to the previous seven questions). The following three questions (I, J, K) refer to quality of life six months after surgery. These questions focus both on health-related well-being and psychological and social wellness. The last question (L) asks the patients whether they would recommend functional arthroplasty to friends and family members affected by the same TMJ pathology. The questions are answered on a 5-point scale (1 = excellent and 5 = poor) [24,36,37,38].
The work has been carried out in accordance with the Declaration of Helsinki. All procedures were performed within the relevant laws and institutional guidelines and have been approved by the Santa Maria Hospital Ethical Committee (TRAUMAX), 3993/19. All the patients who underwent functional arthroplasty surgery signed the informed consent form.
Statistical Analysis
The sample size calculation was performed using a two-tailed paired t-test for the difference between two dependent means, with an effect size of 0.5, an alpha level of 0.05, and a power of 0.85 [38]. The calculation indicated that a minimum of 38 patients would be required to achieve adequate power.
Quantitative variables were analyzed for their distribution using the Kolmogorov–Smirnov test. Based on their asymmetrical distribution, they were represented by the median and interquartile range (IQR), both in the text and graphs. The comparison between two groups was performed using the Wilcoxon rank test, while the comparison among more than two groups was conducted using Friedman’s two-way ANOVA, followed by the Bonferroni post-hoc test. Correlation between scores was assessed using Spearman’s rank test.
Statistical analyses were performed using IBM SPSS Statistics version 29.0.1.0 (IBM, ARMONK, New York, NY, USA), and the graphs were created with GraphPad prism 10.0 (GraphPad software, Inc., La Jolla, CA, USA). The calculation for the sample size was performed using G*power 3.1.9.4., and p < 0.05 was considered statistically significant. Effect sizes were interpreted based on eta-squared (η2) thresholds: small (0.01), medium (0.06), and large (0.14).
3. Results
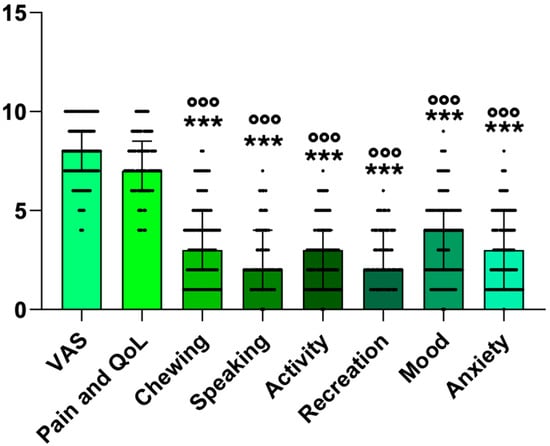
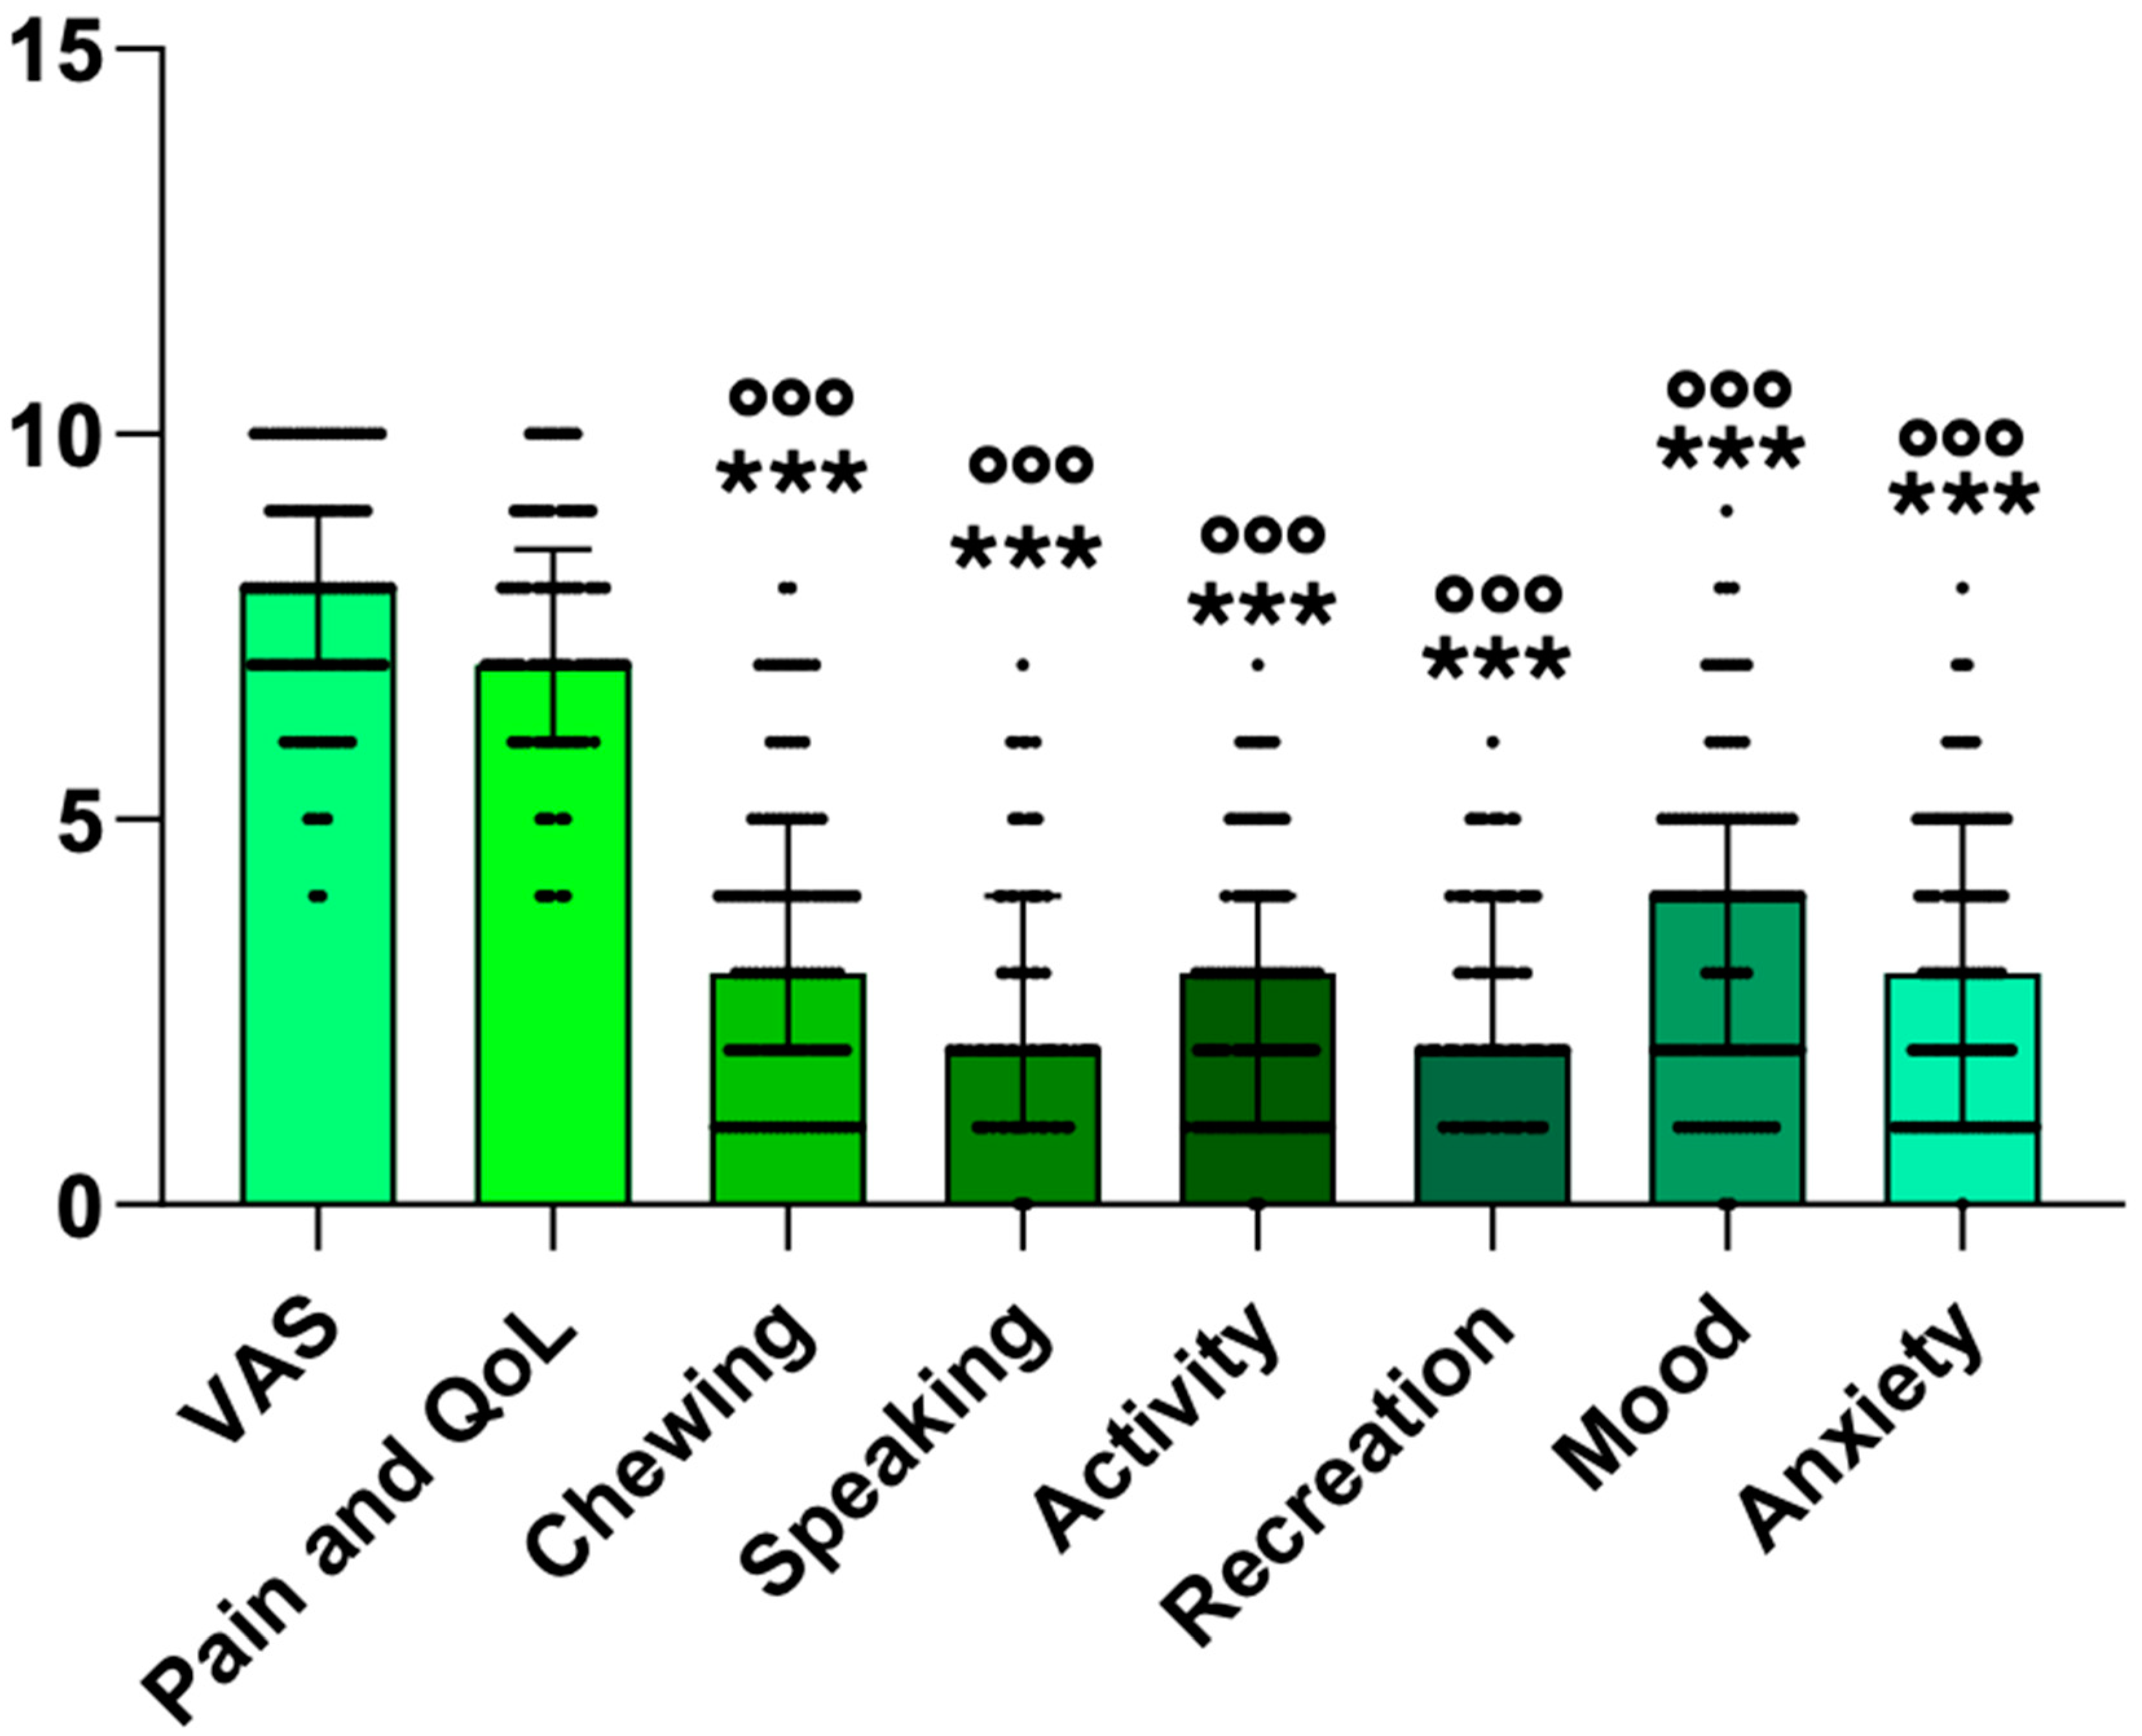
A total of 105 patients with a median age of 38.0 (31.0–51.50) years were identified. A female prevalence (n = 84, 80%) with a male/female ratio of 1:4 was found. The analysis performed on scores before surgery showed that the VAS and pain and quality-of-life scores were significantly higher than all the other scores assessed (large effect size: η2 = 0.53) (Figure 4).
Figure 4.
Scores of patients before surgery. The scatter plots with bars represent the median and interquartile range of scores before surgery. Statistical analysis was performed using Friedman’s two-way test with the Bonferroni post-hoc test. *** = p < 0.001 vs. VAS; °°° = p < 0.001 vs. pain and quality-of-life score.
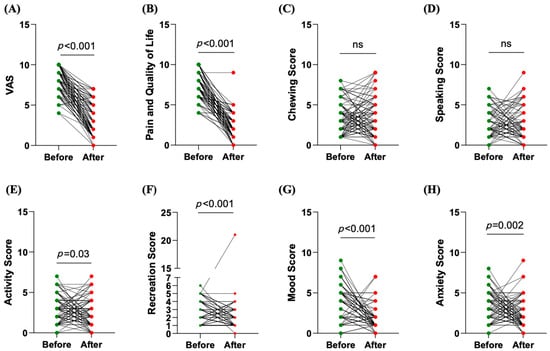
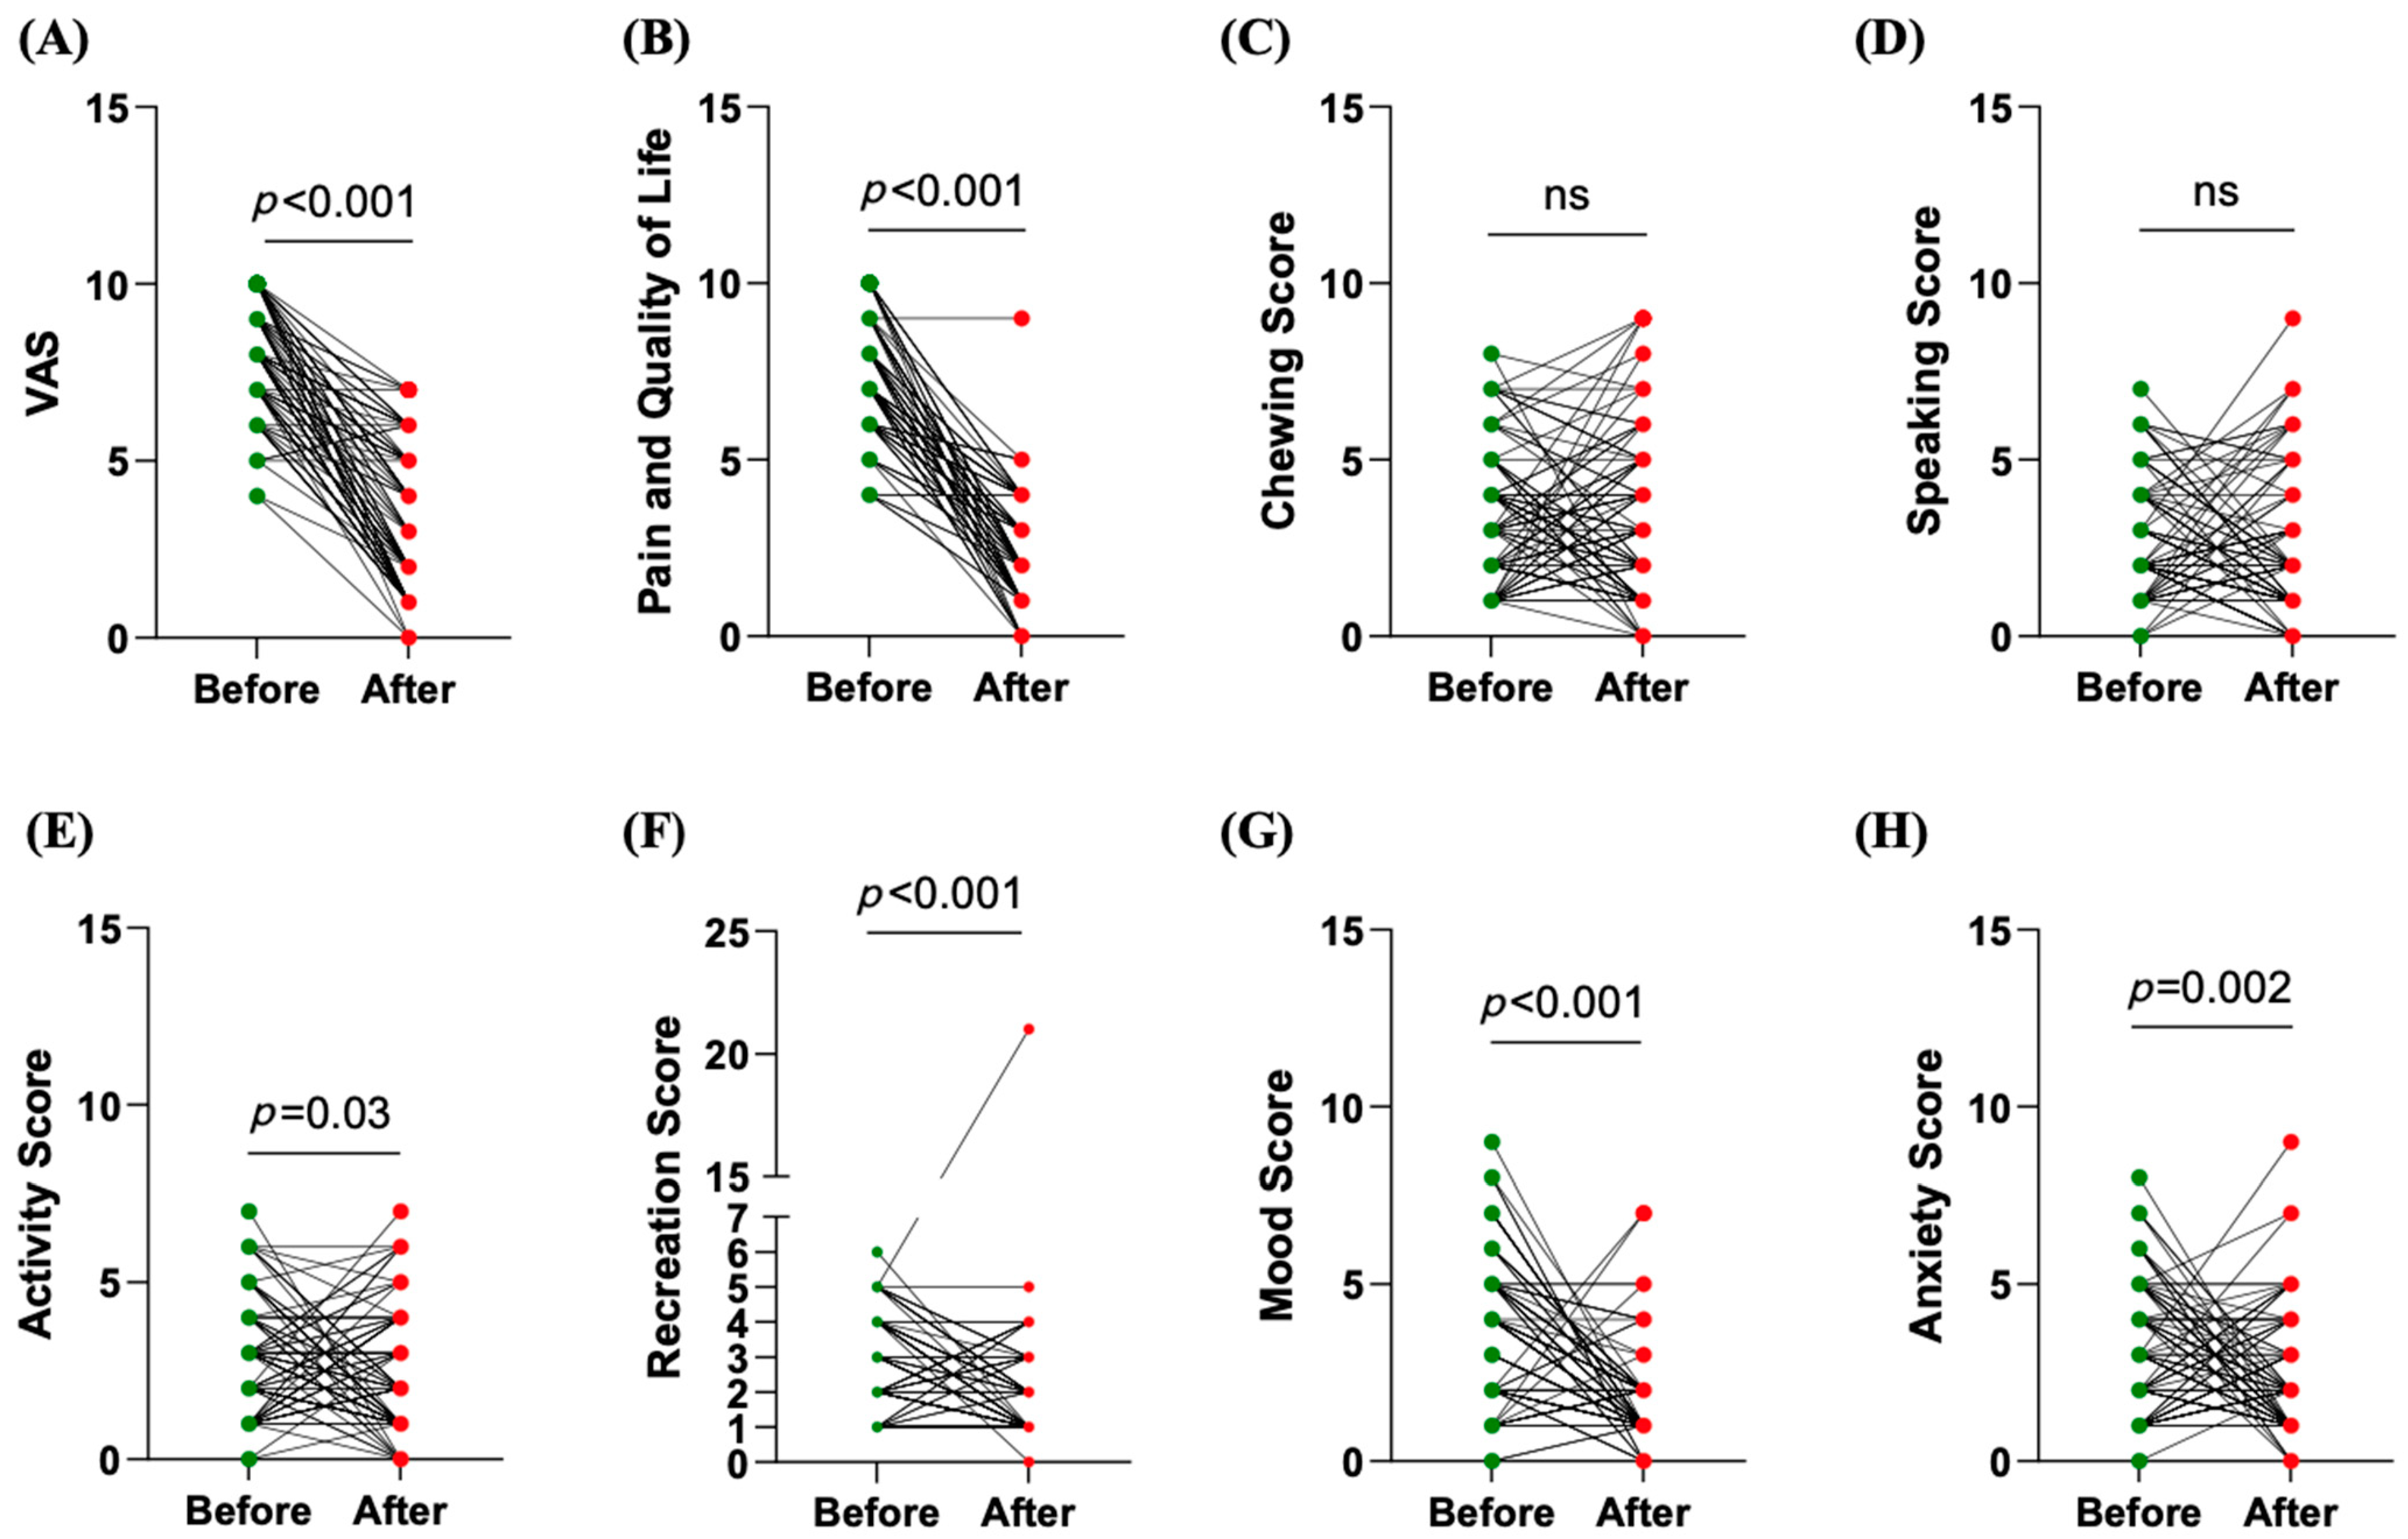
Interestingly, comparing scores before and after surgery, the authors observed a reduction in pain assessed with the VAS (8.0 (7–9) vs. 2.0 (1.0–5.0), η2 = 0.73, p < 0.001) (Figure 5A), pain scores from the quality-of-life (QoL) questionnaire (7.0 (6.0–8.5) vs. 2.0 (1.0–3.0), η2 = 0.74, p < 0.001) (Figure 5B), activity scores (3.0 (1.0–4.0 vs. 2.0 (1.0–4.0), η2 = 0.04, p < 0.05) (Figure 5E), mood scores (4.0 (2.0–5.0) vs. 1.0 (1.0–2.0), η2 = 0.41, p < 0.001) (Figure 5G), and anxiety scores (3.0 (1.0–5.0) vs. 2.0 (1.0–3.0), η2 = 0.09, p < 0.01) (Figure 5H). It should be noted that a significant difference was also found for recreation scores (η2 = 0.18, p < 0.001), despite there being no change in the median value (Figure 5F). This suggests that, while the central tendency remained stable, individual responses varied significantly.
Figure 5.
Comparison of scores before and after surgery. Before–after plots illustrate the distribution of pre- and post-surgical scores, highlighting a statistically significant difference in the VAS (A), pain and quality of life (B), chewing score(C), speaking score (D), activity score (E), recreation score (F), mood score (G), and anxiety score (H). The Wilcoxon test was applied.
On the contrary, no differences were found for the chewing and speaking scores before and after surgery in our cohort (Figure 5C,D).
Spearman’s rank correlation analysis showed no correlation between scores before surgery. However, the same analysis performed only on the scores that were significantly reduced after surgery showed a slight but significant positive correlation between pain assessed with the VAS, pain scores from the QoL questionnaire, and mood scores (Table 2). In addition, a slight but significant negative correlation between the activity scores and both pain assessed with the VAS and pain scores from the QoL questionnaire as well as between the mood and recreation scores was detected (Table 2).
Table 2.
Results of Spearman’s rank correlation analysis of the relationship between scores after surgery.
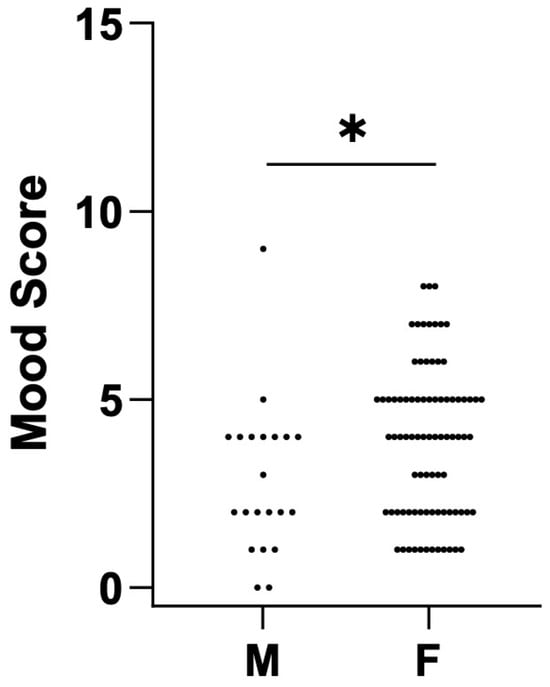
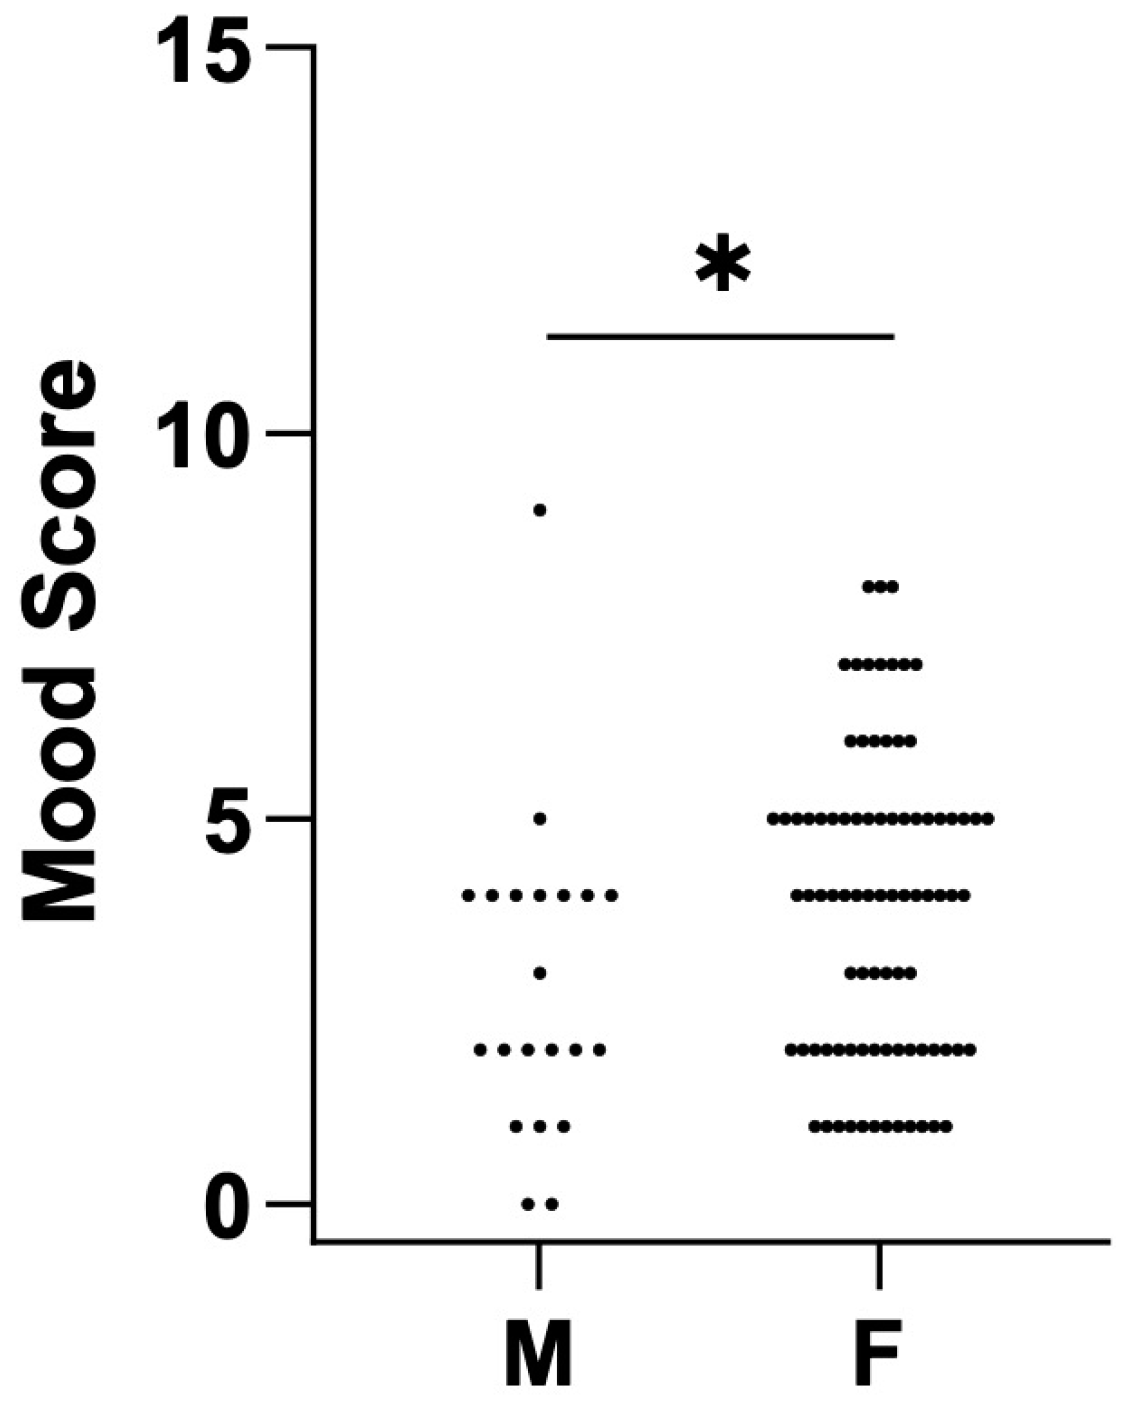
No differences in scores were observed before and after surgery between patients aged ≤ 38 years and those aged > 38 years. Comparing females and males, we found a statistically significant difference at baseline in mood scores. Specifically, a higher score, corresponding to a worse mood, was seen in females compared to males (4 (2–5) vs. 2 (1.5–4), p < 0.05) (Figure 6). However, no differences were observed post-surgery.
Figure 6.
Worse mood scores for females before surgery. The scatter plot represents the distribution of mood scores for males and females before surgery. Statistical analysis was performed by the Wilcoxon test. * = p < 0.05.
4. Discussion
Anterior disc displacement without reduction (ADDwoR) of the temporomandibular joint (TMJ) often leads to persistent pain and reduced quality of life (QoL). Conservative treatments frequently fail to provide adequate symptom relief.
The authors aimed to assess the hypothesis that functional arthroplasty is a short-term (≥6 months) effective treatment for reducing pain and improving QoL in patients with ADDwoR unresponsive to conservative therapies.
The authors identified a total of 105 patients with a median age of 38.0 years. The cohort exhibited a significant female predominance (80%). This skewed gender distribution has already been confirmed in the literature [2,35,39].
The initial analysis focused on pre-surgery scores, revealing that pain assessed with the VAS and pain scores from the QoL questionnaire were significantly higher than all the other measured scores. This indicates that pain and its effect on quality of life were the most affected domains in these patients before undergoing surgery.
Upon comparing the scores before and after surgery, there was a marked reduction in several key areas. Substantial decreases were registered for pain assessed with the VAS and pain scores from the QoL questionnaire, highlighting the effectiveness of the surgical intervention in alleviating pain and improving the overall quality of life for these patients. Other scores also demonstrated significant improvements post-surgery, such as the activity, mood, and anxiety scores. In addition, the recreation score saw a significant but small reduction. This might be explained by the fact that a low score was already observed before surgery, underlining that these recreational activities are one of the areas less compromised in this type of patient. Surprisingly, the chewing and speaking scores did not show significant differences before and after surgery. It should be noted that these two scores, along with recreation scores, were among the lowest scores recorded before surgery. Nevertheless, this result suggests that surgical intervention did not impact these specific functions.
Spearman’s rank correlation analysis provided further insights into the relationships between different scores. Before surgery, no correlations were observed; however, after surgery, several slight but significant positive and negative correlations emerged. For instance, a positive correlation was found between pain assessed with the VAS and pain scores from the QoL questionnaire, indicating that patients who experienced a decrease in pain after surgery also reported an enhancement in their quality of life. Moreover, the mood score was found to be positively correlated with pain assessed with the VAS, demonstrating how the reduction in pain after surgery positively influenced mood. Interestingly, pain assessed with the VAS and pain scores from the QoL questionnaire negatively correlated with the activity score, highlighting how the reduction in pain and its effect on QoL also leads to an improvement in the ability to perform activities. These findings suggest interdependencies between different aspects of patient well-being, with improvements in one area being associated with improvements in another. However, a better mood was associated with a worse ability to perform daily activities.
The adopted surgical technique, named functional arthroplasty, is based on three principles: condylar shaving, disc repositioning, and fixation with the reconstruction of the lateral ligament. It is the authors’ opinion that condylar shaving produces the following results: (a) it eliminates the condylar irregularity observed in the case of long-lasting disc displacement; (b) it widens the articular space, which has been reduced by vertical height loss; (c) it creates scar adhesions between the disc and condyle, thus leading to greater stability post-surgery [29,30,31,32,39,40].
To the authors’ knowledge, this is the first study in the literature to assess improvements in quality of life after functional arthroplasty using the QoL-TMJ questionnaire.
Subjective methods to assess the patient’s perception of the clinical condition are fundamental to fully understanding the role of functional arthroplasty in improvements to the patient’s quality of life and general approach to daily living. Despite this, it is important to understand that pain perception and its impact on life differs among patients because of the pain threshold variability.
The main limitation of this study is the subjectivity of the answers, resulting from the fact that patients have different levels of adaptation, pain endurance, and resilience beyond the surgical technique used and the relatively small sample.
In conclusion, functional arthroplasty offers a robust solution for managing persistent TMJ pain and its associated impacts on daily life, paving the way for enhanced patient well-being. Future research should focus on long-term outcomes and further validate the sustained benefits of this surgical technique, as well as exploring strategies to address unchanged functional aspects like chewing and speaking.
5. Conclusions
This study demonstrates that functional arthroplasty is an effective surgical intervention for patients with anterior disc displacement without reduction (ADDwoR) who have not responded to non-surgical or minimally invasive treatments. The procedure significantly reduces pain, as evidenced by a marked decrease in pain (VAS score), and substantially improves overall quality of life, including key aspects such as mood, activity level, and anxiety.
Interestingly, despite the significant alleviation of pain and enhancement of life quality, the procedure did not impact chewing and speaking abilities, indicating these functions were less affected by the pathology or were possibly resistant to change post-surgery. The strong correlations observed between improvements in pain, mood, and quality of life underscore the interconnected nature of these domains, highlighting the comprehensive benefits of functional arthroplasty.
Notably, the intervention was equally effective across different genders and age groups, reinforcing its broad applicability. However, the study also revealed a higher baseline level of mood disturbance in females, a finding not widely discussed in the existing literature. This gender-specific difference emphasizes the need for tailored pre-surgical assessments and interventions.
Author Contributions
Conceptualization, F.S. and V.V.; methodology, V.V.; formal analysis, G.C.; investigation, S.D.T.; data curation, G.C.; writing—original draft preparation, S.D.T.; writing—review and editing, V.V.; visualization, L.A.V. and D.F.A.; supervision, V.V. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki and approved by the Ethics Committee of Santa Maria Hospital Ethical Committee (TRAUMAX), No. 3993; approval date: 24 January 2018.
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study. Written informed consent has been obtained from the patients to publish this paper.
Data Availability Statement
Data is unavailable due to privacy.
Conflicts of Interest
The authors declare no conflicts of interest.
Abbreviations
The following abbreviations are used in this manuscript:
| ADDwoR | anterior disc displacement without reduction |
| IQR | interquartile range |
| MMO | maximum assisted opening movement |
| QoL | quality of life |
References
- Dimitroulis, G.; McCullough, M.; Morrison, W. Quality-of-Life Survey Comparing Patients before and after Discectomy of the Temporomandibular Joint. J. Oral Maxillofac. Surg. 2010, 68, 101–106. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stern, I.; Greenberg, M.S. Clinical Assessment of Patients with Orofacial Pain and Temporomandibular Disorders. Dent. Clin. N. Am. 2013, 57, 393–404. [Google Scholar] [CrossRef] [Scilit]
- Mercuri, L.G. Temporomandibular Joint Disorder Management in Oral and Maxillofacial Surgery. J. Oral Maxillofac. Surg. 2017, 75, 927–930. [Google Scholar] [CrossRef] [Scilit]
- Felin, G.C.; Tagliari, C.V.d.C.; Agostini, B.A.; Collares, K. Prevalence of Psychological Disorders in Patients with Temporomandibular Disorders: A Systematic Review and Meta-Analysis. J. Prosthet. Dent. 2024, 132, 392–401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Miloro, M.; Ghali, E.G.; Larsen, E.P.; Waite, P. Peterson’s Principles of Oral and Maxillofacial Surgery, 4th ed.; Springer: Berlin/Heidelberg, Germany, 2022. [Google Scholar]
- Zieliński, G.; Pająk-Zielińska, B.; Ginszt, M. A Meta-Analysis of the Global Prevalence of Temporomandibular Disorders. J. Clin. Med. 2024, 13, 1365. [Google Scholar] [CrossRef] [Scilit]
- Manfredini, D.; Guarda-Nardini, L.; Winocur, E.; Piccotti, F.; Ahlberg, J.; Lobbezoo, F. Research Diagnostic Criteria for Temporomandibular Disorders: A Systematic Review of Axis I Epidemiologic Findings. Oral Surg. Oral Med. Oral Pathol. Oral Radiol. Endod. 2011, 112, 453–462. [Google Scholar] [CrossRef] [Scilit]
- Blankestijn, J.; Boering, G. Posterior Dislocation of the Temporomandibular Disc. Int. J. Oral Surg. 1985, 14, 437–443. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Westesson, P.L.; Larheim, T.A.; Tanaka, H. Posterior Disc Displacement in the Temporomandibular Joint. J. Oral Maxillofac. Surg. 1998, 56, 1266–1273. [Google Scholar] [CrossRef] [Scilit]
- Brooks, S.L.; Westesson, P.L. Temporomandibular Joint: Value of Coronal MR Images. Radiology 1993, 188, 317–321. [Google Scholar] [CrossRef] [Scilit]
- Katzberg, R.W.; Westesson, P.L.; Tallents, R.H.; Anderson, R.; Kurita, K.; Manzione, J.V.; Totterman, S. Temporomandibular Joint: MR Assessment of Rotational and Sideways Disk Displacements. Radiology 1988, 169, 741–748. [Google Scholar] [CrossRef] [Scilit]
- De la Torre Canales, G.; Manfredini, D.; Grillo, C.M.; Guarda-Nardini, L.; Machado Gonçalves, L.; Rizzatti Barbosa, C.M. Therapeutic Effectiveness of a Combined Counseling plus Stabilization Appliance Treatment for Myofascial Pain of the Jaw Muscles: A Pilot Study. Cranio 2017, 35, 180–186. [Google Scholar] [CrossRef] [Scilit]
- Wänman, A.; Marklund, S. Treatment Outcome of Supervised Exercise, Home Exercise and Bite Splint Therapy, Respectively, in Patients with Symptomatic Disc Displacement with Reduction: A Randomised Clinical Trial. J. Oral Rehabil. 2020, 47, 143–149. [Google Scholar] [CrossRef] [Scilit]
- Montinaro, F.; Nucci, L.; d’Apuzzo, F.; Perillo, L.; Chiarenza, M.C.; Grassia, V. Oral Nonsteroidal Anti-Inflammatory Drugs as Treatment of Joint and Muscle Pain in Temporomandibular Disorders: A Systematic Review. Cranio 2024, 42, 641–650. [Google Scholar] [CrossRef] [Scilit]
- Singh, S.; Prasad, R.; Punga, R.; Datta, R.; Singh, N. A Comparison of the Outcomes Following Intra-Articular Steroid Injection Alone or Arthrocentesis Alone in the Management of Internal Derangement of the Temporomandibular Joint. Natl. J. Maxillofac. Surg. 2022, 13, S80–S84. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sidebottom, A.J. Current Thinking in Temporomandibular Joint Management. Br. J. Oral Maxillofac. Surg. 2009, 47, 91–94. [Google Scholar] [CrossRef] [Scilit]
- McKenna, S.J. Discectomy for the Treatment of Internal Derangements of the Temporomandibular Joint. J. Oral Maxillofac. Surg. 2001, 59, 1051–1056. [Google Scholar] [CrossRef] [Scilit]
- Miloro, M.; Henriksen, B. Discectomy as the Primary Surgical Option for Internal Derangement of the Temporomandibular Joint. J. Oral Maxillofac. Surg. 2010, 68, 782–789. [Google Scholar] [CrossRef] [Scilit]
- Mohanty, S.; Vijayaragavan, R.; Sharma, P.; Chaudhary, Z.; Verma, A.; Rathaur, A. Is Modified Condylotomy a Better Surgical Option Compared With High-Condylar Shave With Eminectomy in Improving Symptoms of Internal Derangement of Temporomandibular Joint? J. Oral Maxillofac. Surg. 2022, 80, 1158–1173. [Google Scholar] [CrossRef] [Scilit]
- Lee, B.K.; Hong, J.H. Temporomandibular Joint Disc Plication with MITEK Mini Anchors: Surgical Outcome of 65 Consecutive Joint Cases Using a Minimally Invasive Approach. Maxillofac. Plast. Reconstr. Surg. 2020, 42, 14. [Google Scholar] [CrossRef] [Scilit]
- Abdelrehem, A.; Hu, Y.K.; Yang, C.; Zheng, J.S.; Shen, P.; Shen, Q.C. Arthroscopic versus Open Disc Repositioning and Suturing Techniques for the Treatment of Temporomandibular Joint Anterior Disc Displacement: 3-Year Follow-up Study. Int. J. Oral Maxillofac. Surg. 2021, 50, 1351–1360. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gonçalves, J.R.; Cassano, D.S.; Rezende, L.; Wolford, L.M. Disc Repositioning: Does It Really Work? Oral Maxillofac. Surg. Clin. N. Am. 2015, 27, 85–107. [Google Scholar] [CrossRef] [Scilit]
- Alakailly, X.; Schwartz, D.; Alwanni, N.; Demko, C.; Altay, M.A.; Kilinc, Y.; Baur, D.A.; Quereshy, F. Patient-Centered Quality of Life Measures after Alloplastic Temporomandibular Joint Replacement Surgery. Int. J. Oral Maxillofac. Surg. 2017, 46, 204–207. [Google Scholar] [CrossRef] [Scilit]
- Cascone, P.; Spallaccia, F.; Vellone, V. Temporomandibular Joint Surgery: Open Discopexy and “Functional Arthroplasty”. Atlas Oral Maxillofac. Surg. Clin. N. Am. 2022, 30, 193–198. [Google Scholar] [CrossRef] [Scilit]
- He, D.; Yang, C.; Zhang, S.; Wilson, J.J. Modified Temporomandibular Joint Disc Repositioning with Miniscrew Anchor: Part I--Surgical Technique. J. Oral Maxillofac. Surg. 2015, 73, e1–e47. [Google Scholar] [CrossRef] [Scilit]
- Schiffman, E.; Ohrbach, R.; Truelove, E.; Look, J.; Anderson, G.; Goulet, J.-P.; List, T.; Svensson, P.; Gonzalez, Y.; Lobbezoo, F.; et al. Diagnostic Criteria for Temporomandibular Disorders (DC/TMD) for Clinical and Research Applications: Recommendations of the International RDC/TMD Consortium Network* and Orofacial Pain Special Interest Group†. J. Oral Facial Pain Headache 2014, 28, 6–27. [Google Scholar] [CrossRef] [Scilit]
- Wilkes, C.H. Internal Derangements of the Temporomandibular Joint: Pathological Variations. Arch. Otolaryngol. Head Neck Surg. 1989, 115, 469–477. [Google Scholar] [CrossRef] [Scilit]
- Ângelo, D.F. A Letter to the Editor on “Root of Helix Inter Tragus Notch Incision (RHITNI) for Temporomandibular Open Surgery”. Int. J. Surg. 2020, 83, 233–234. [Google Scholar] [CrossRef] [Scilit]
- Kirk, W.S. Illustrated Surgical Techniques for Management of Impingements of the Temporomandibular Joint. Int. J. Oral Maxillofac. Surg. 2013, 42, 229–236. [Google Scholar] [CrossRef] [Scilit]
- Mehra, P.; Wolford, L.M. The Mitek Mini Anchor for TMJ Disc Repositioning: Surgical Technique and Results. Int. J. Oral Maxillofac. Surg. 2001, 30, 497–503. [Google Scholar] [CrossRef] [Scilit]
- Spallaccia, F.; Rivaroli, A.; Basile, E.; Cascone, P. Disk Repositioning Surgery of the Temporomandibular Joint with Bioabsorbable Anchor. J. Craniofac. Surg. 2013, 24, 1792–1795. [Google Scholar] [CrossRef] [Scilit]
- Weymuller, E.A.; Alsarraf, R.; Yueh, B.; Deleyiannis, F.W.B.; Coltrera, M.D. Analysis of the Performance Characteristics of the University of Washington Quality of Life Instrument and Its Modification (UW-QOL-R). Arch. Otolaryngol. Head Neck Surg. 2001, 127, 489–493. [Google Scholar] [CrossRef] [Scilit]
- Carter, M.J.; Ellis, O.G.; Tocaciu, S.; McCullough, M.J.; Dimitroulis, G. A 2-Year Comparison of Quality of Life Outcomes between Biomet Stock and OMX Custom Temporomandibular Joint Replacements. Adv. Oral Maxillofac. Surg. 2022, 5, 100221. [Google Scholar] [CrossRef] [Scilit]
- Dimitroulis, G. Comparison of the Outcomes of Three Surgical Treatments for End-Stage Temporomandibular Joint Disease. Int. J. Oral Maxillofac. Surg. 2014, 43, 980–989. [Google Scholar] [CrossRef] [Scilit]
- Bjerre-Bastos, J.J.; Miller, C.P.; Li, Y.; Andersen, J.R.; Karsdal, M.; Bihlet, A.R. Associations between Single-Question Visual Analogue Scale Pain Score and Weight-Bearing and Non-Weight-Bearing Domains of Western Ontario and McMaster Universities Arthritis Index Pain: Data from 2 Phase 3 Clinical Trials. Pain Rep. 2022, 7, 1017. [Google Scholar] [CrossRef] [Scilit]
- Wang, X.; Fang, X.; Qi, B.; Xiao, W.; Pan, Z.; Xie, Z. Comparing the Efficacy of Anatomical Locked Plate Fixation with Coracoclavicular Ligament Augmentation to Hook Plate Fixation in Treating Distal Clavicle Fractures. Orthop. Surg. 2022, 14, 3358–3366. [Google Scholar] [CrossRef] [Scilit]
- Rehme, C.; Fritsch, B.; Thomas, L.; Istin, S.; Burchert, C.; Hummel, B.; Baleanu-Curaj, B.; Reis, H.; Szarvas, T.; Ruebben, H.; et al. Clinical Outcome and Quality of Life in Octogenarian Patients with Muscle-Invasive Urothelial Carcinoma of the Bladder Treated with Radical Cystectomy or Transurethral Resection of the Bladder Tumor: A Retrospective Analysis of 143 Patients. Int. Urol. Nephrol. 2022, 54, 71–79. [Google Scholar] [CrossRef] [Scilit]
- Althubaiti, A. Sample Size Determination: A Practical Guide for Health Researchers. J. Gen. Fam. Med. 2022, 24, 72–78. [Google Scholar] [CrossRef] [Scilit]
- Cascone, P.; Ramieri, V.; Arangio, P.; Vellone, V.; Tarsitano, A.; Marchetti, C. TMJ Inferior Compartment Arthroplasty Procedure through a 25-Year Follow-up (Functional Arthroplasty). Ann. Stomatol. 2016, 7, 60–64. [Google Scholar] [CrossRef] [Scilit]
- Spallaccia, F.; Vellone, V.; Colangeli, W.; De Tomaso, S. Maxillofacial Fractures in the Province of Terni (Umbria, Italy) in the Last 11 Years: Impact of COVID-19 Pandemic. J. Craniofac. Surg. 2022, 33, E853–E858. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).