


Abstract
Introduction: Gestational diabetes mellitus (GDM) is a form of hyperglycemia that develops during pregnancy and poses risks to both the mother and fetus. In other words, it is a glucose intolerance disorder first recognized during pregnancy, specifically in the second and third trimesters, with approximately 7–14% of pregnancies worldwide being affected. Methodology: A systematic literature search was conducted across three major well-established databases; PubMed, Scopus, and ScienceDirect. The search was conducted with the aim of identifying the most suitable studies for the evaluation of fetal cardiac function using Doppler ultrasound techniques in pregnancies affected by GDM. Results: Following a comprehensive full-text assessment, 186 papers were excluded, mainly due to discrepancies in the population, unsuitable study design, publishing type, or unavailability of full-text access. Ultimately, 12 studies met all the inclusion criteria and were incorporated into the scoping review. From the studies included it was found that the conventional pulsed-wave Doppler was the most frequently used modality, assessing parameters such as the E/A ratios, myocardial performance index (MPI), and the isovolumic relaxation time (IVRT). The advanced techniques of choice included tissue Doppler imaging (TDI), speckle-tracking echocardiography (STE), dual-gate Doppler, and automated MPI. Conclusions: Doppler ultrasound techniques, particularly the advanced modalities like TDI and STE, provide valuable insights into fetal cardiac function in GDM pregnancies. Their integration into routine prenatal surveillance may enhance the early detection of cardiac dysfunction and inform timely clinical interventions.
1. Introduction
Gestational diabetes mellitus (GDM) is a form of hyperglycemia that develops during pregnancy and poses risks to both the mother and the fetus. In other words, it is a glucose intolerance disorder first recognized during pregnancy, specifically in the second and third trimesters, with approximately 7–14% of pregnancies worldwide being affected. The prevalence of GDM development is further rising along with parallel risk factors such as maternal obesity and advanced maternal age [1,2,3]. While GDM is often thought of as being a transient condition, affecting the mother only throughout the gestational period, it has now been associated with an increased risk of cardiovascular disease (CVD) later in the life of the mother. The risk extends beyond the development of type 2 diabetes to include illnesses such as coronary artery disease, myocardial infarction, stroke, and heart failure [4,5]. More specifically, a meta-analysis found that a history of GDM was associated with a 2-fold higher risk of total cardiovascular disease [6]. Another study conducted by Yu Y. et al. (2022) revealed that women with a history of GDM had a 40% increased overall CVD risk [7]. On the other hand, fetal exposure to maternal hyperglycemia leads to a cascade of metabolic and hormonal disturbances, including fetal hyperinsulinemia, oxidative stress, and altered placental signaling, which collectively contribute to cardiac remodeling and functional impairment. The fetal response to maternal hyperglycemia is determined by various factors, including the severity and timing of exposure, metabolic abnormalities, and genetic predisposition. These reactions can cause transcriptional and epigenetic alterations throughout the critical stages of heart development [8,9].
Given the nature of these cardiac alterations, Doppler-based ultrasound techniques have emerged as essential tools allowing for the non-invasive, real-time evaluation of blood flow within the fetal heart, which can reveal subtle and dynamic changes indicative of potential cardiac abnormalities [10,11,12].
Objective
The objective of this scoping review is to systematically examine, map, and evaluate the use of Doppler-based ultrasound techniques for assessing fetal cardiac function in utero in pregnancies complicated by GDM. Specifically, this review aims to (1) identify the range of Doppler modalities and parameters applied, (2) assess their reported diagnostic value and clinical relevance, and (3) highlight methodological gaps and areas for future research. By synthesizing the current evidence, this review seeks to inform the development of evidence-based guidelines for fetal cardiac surveillance in GDM and contribute to improved perinatal cardiovascular outcomes.
2. Methodology
A systematic mapping of the literature on GDM-related fetal cardiac outcomes was undertaken rather than a formal meta-analysis, owing to the marked heterogeneity in study designs, diagnostic criteria, imaging modalities, and outcome measures. This study adhered to the PRISMA-ScR (Preferred Reporting Items for Systematic reviews and Meta-Analyses extension for Scoping Reviews) checklist to ensure transparent and comprehensive reporting (Table S1). Due to the nature of the study no PROSPERO registration was required for its execution.
2.1. Search Strategy
A systematic literature search was conducted across three major well-established databases; PubMed, Scopus, and ScienceDirect. The search was conducted with the aim of identifying the most suitable studies for the evaluation of fetal cardiac function using Doppler ultrasound techniques in pregnancies affected by GDM. We constructed a single search statement combining Medical Subject Headings (MeSH) and free-text terms with the operators AND and OR (a Boolean search strategy), including the variations highlighted in Table 1. This ensures that each concept is fully captured while minimizing irrelevant records.
Table 1.
Search strategy and terms used in PubMed, Scopus, and ScienceDirect.
2.2. Research Question and Eligibility Criteria
The research question was outlined more clearly using the Population, Intervention/Exposure, Comparator, Outcome (PICO) framework.
- P (Population): Fetuses of pregnant women diagnosed with gestational diabetes mellitus (GDM).
- I (Intervention/Exposure): Doppler-based fetal echocardiographic techniques.
- C (Comparator): Fetuses of pregnant women with normoglycemic pregnancies (non-diabetic controls) or within-group comparisons (well vs. poorly controlled GDM).
- O (Outcomes): Alterations in fetal cardiac structure and function, such as the myocardial performance index (MPI), E/A and E′/A′ ratios, cardiac output, ventricular wall thickness, global longitudinal strain (GLS), diastolic/systolic dysfunction indices, and predictive value for adverse perinatal outcomes.
The following eligibility criteria were created to complement the PICO framework and guide the reviewers in the screening process, ensuring that the chosen articles correctly addressed the research question.
2.3. Inclusion Criteria
Human studies involving pregnancies complicated by GDM;
- Use of Doppler ultrasound (spectral, tissue, or advanced techniques) for assessment of fetal cardiac function or structure;
- Original research articles, including randomized controlled trials, prospective or retrospective cohort, and case-control studies;
- Availability of full-text articles published in English.
2.4. Exclusion Criteria
- Studies involving only non-GDM populations;
- Animal or in vitro studies;
- Secondary literature (reviews, editorials, commentaries);
- Conference papers and abstracts;
- Articles lacking full-text access or methodological transparency.
2.5. Screening Process
The search process was independently performed by two reviewers as a blind process (S.T. and I.K.), coordinated at all stages of screening and data extraction to ensure methodological consistency and accuracy. Any conflicts were resolved during the second stage of the screening process by a third reviewer (A.M.).
2.6. Data Extraction Process
Data from the final studies included in this scoping review were extracted using structured Microsoft Excel tables. A predefined framework was employed to guide the extraction process, with the objective of capturing the essential study characteristics and outcomes. The initial author and year of publication, study design (cohort, cross-sectional, randomized controlled trial), population characteristics (including gestational age range and diagnostic criteria for GDM), type of Doppler technique used (spectral Doppler, tissue Doppler imaging, color Doppler, fetal HQ), and the key findings related to fetal cardiac structure and/or function were recorded for each study. This standardized approach ensured consistency across the dataset and facilitated the thematic synthesis and comparative analysis during the review process.
3. Results
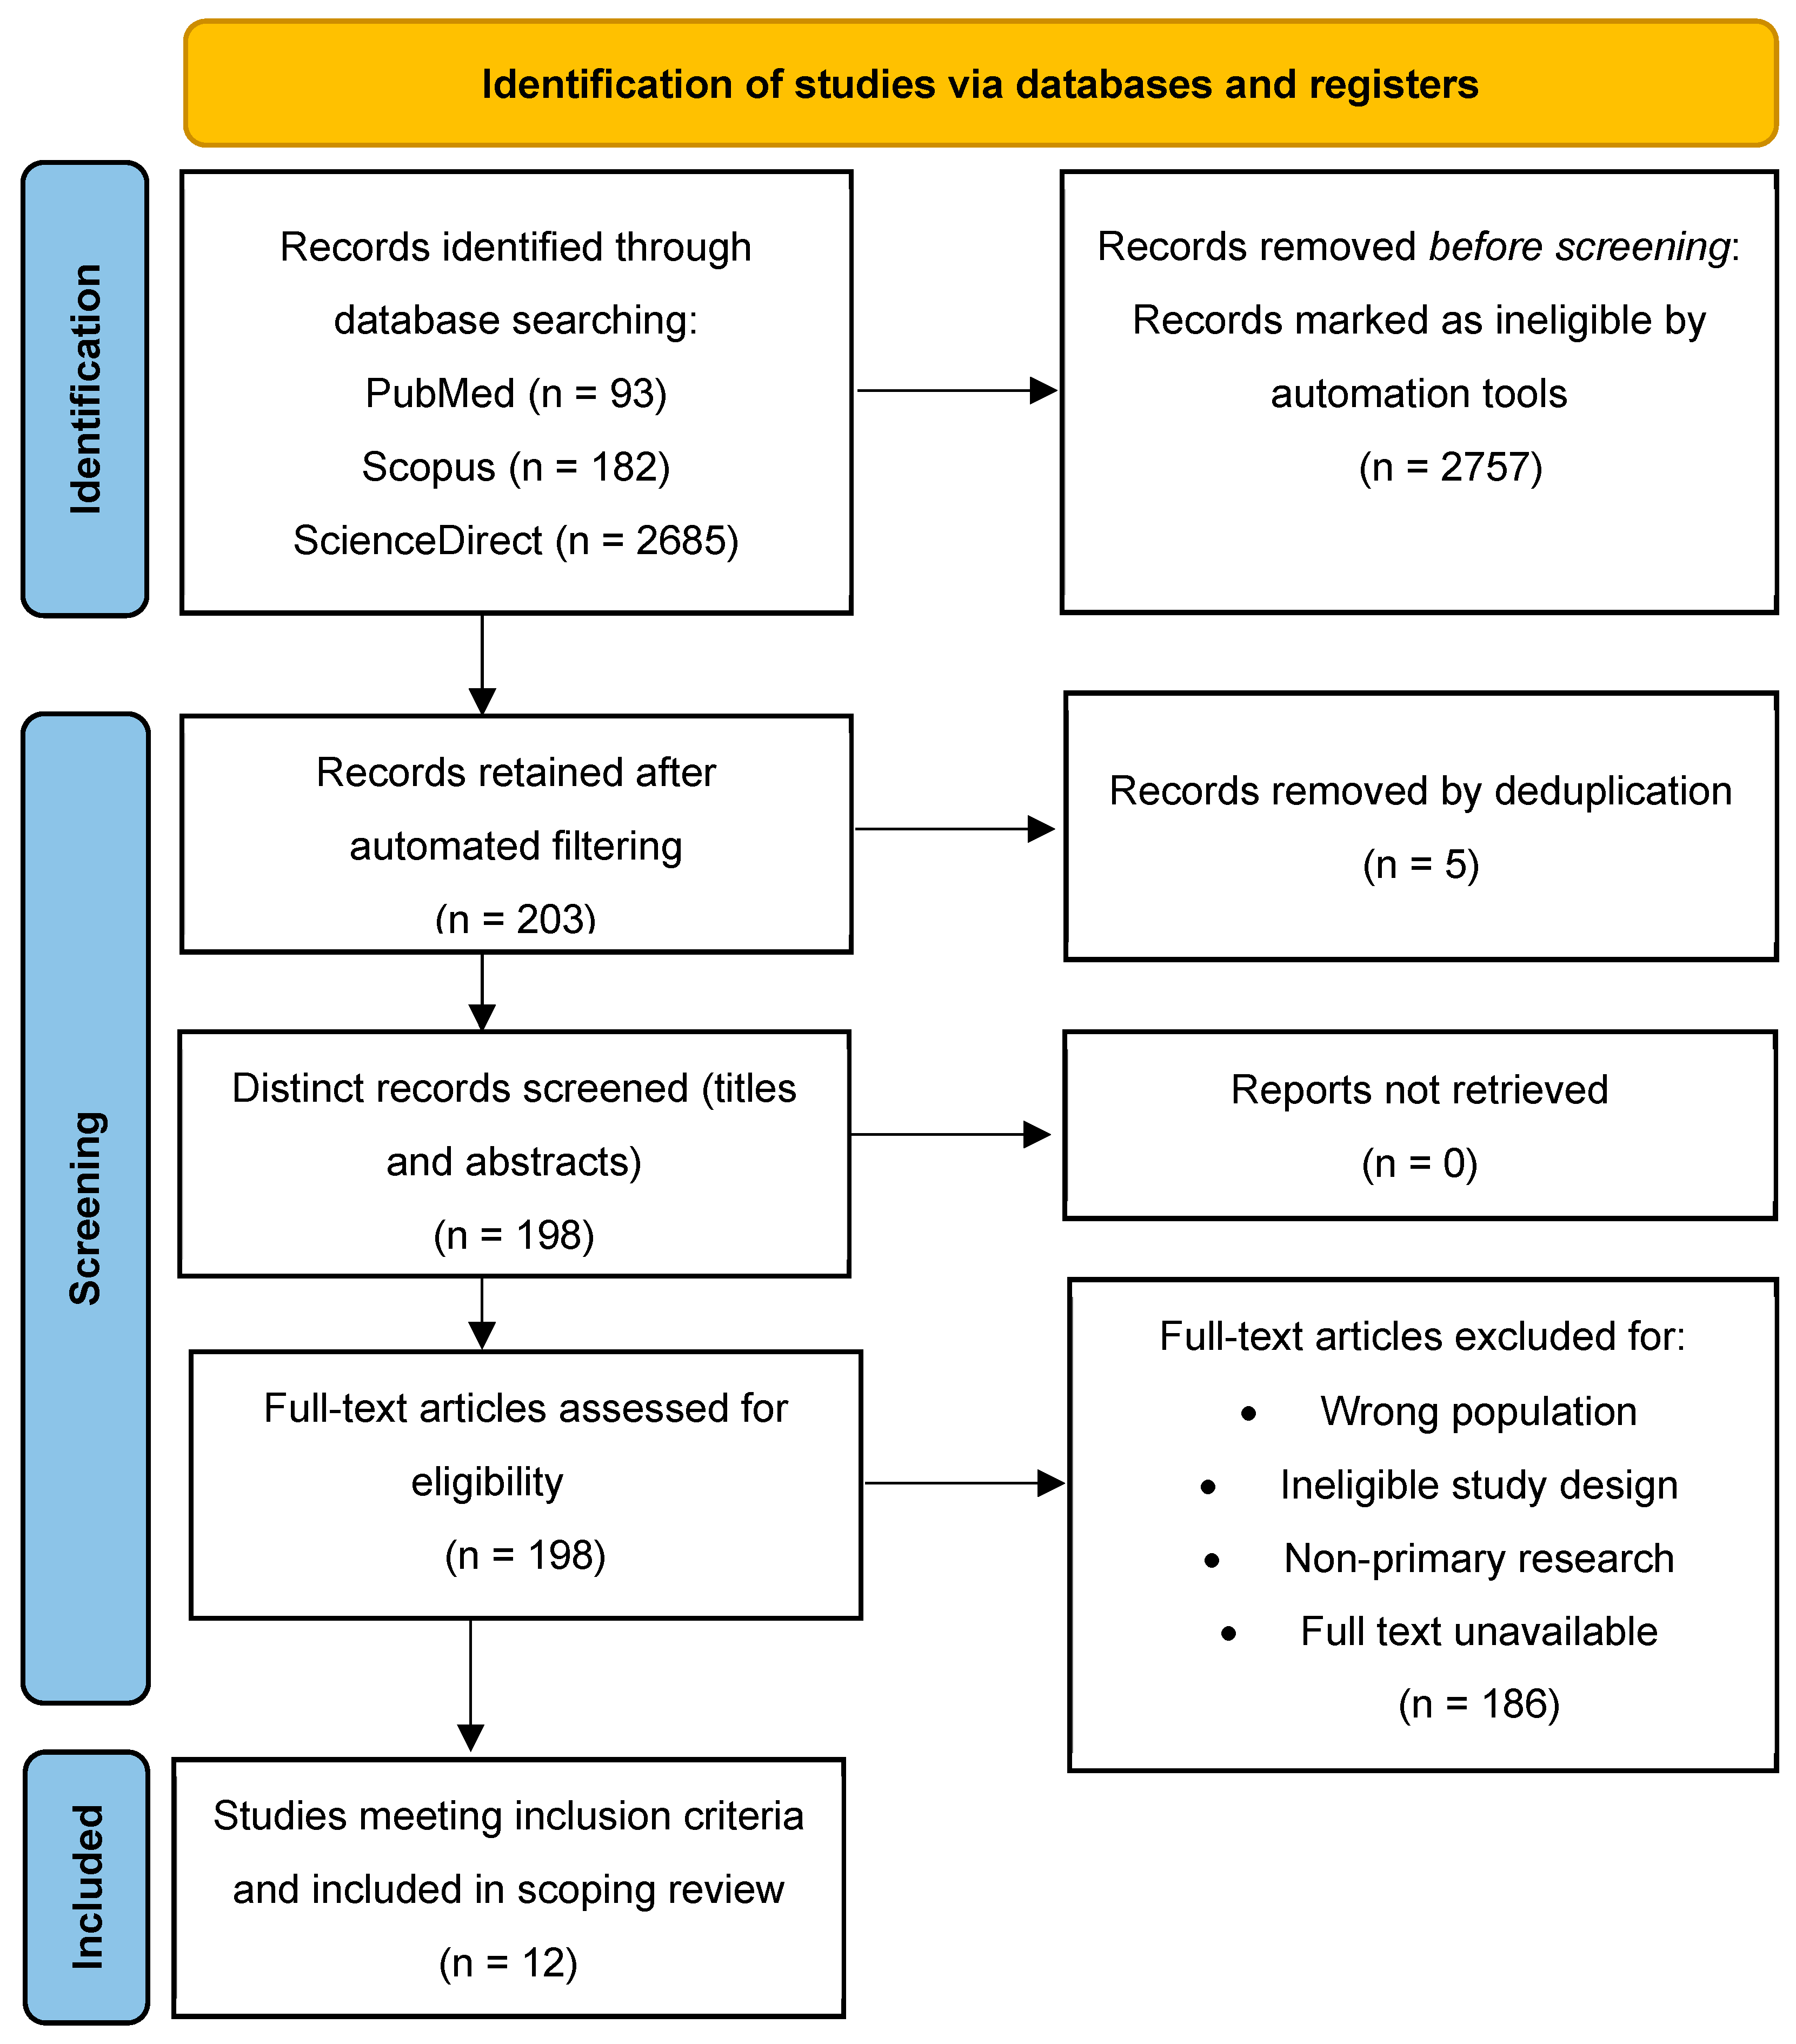
The initial search identified records in PubMed (n = 93), Scopus (n = 182), and ScienceDirect (n = 2685), yielding a combined total of 2960 articles. After the employment of automated tools for filtering and deduplication with reference management software, 203 records were retained for screening. Five (5) duplicate entries were eliminated, and 198 distinct research papers remained for screening.
Following a comprehensive full-text assessment, 186 papers were excluded, mainly due to discrepancies in the population, unsuitable study design, publishing type, or the unavailability of full-text access. Ultimately, 12 studies met all the inclusion criteria and were incorporated into the scoping review. The PRISMA flow diagram is shown in Figure 1 and the summary table with the findings from each study is found in Table 2.
Figure 1.
PRISMA flow diagram.
Table 2.
Summary of Doppler-based studies evaluating fetal cardiac structure and function in diabetic pregnancies.
The included studies employed a range of Doppler-based ultrasound techniques for the assessment of fetal cardiac function during gestation that was complicated by the presence of GDM.
3.1. Conventional Pulsed-Wave Doppler
Three studies utilized pulsed-wave Doppler to evaluate the E/A ratios, the myocardial performance index (MPI), and the isovolumic relaxation time (IVRT). These parameters consistently revealed diastolic dysfunction in the fetuses of GDM mothers, with elevated MPI and reduced E/A ratios, even in the absence of structural abnormalities or poor glycemic control [13,14,15].
3.2. Modified and Automated MPI
Additionally, the modified MPI (Mod-MPI), which uses valve clicks for improved reproducibility, was revealed to be a sensitive predictor of adverse perinatal outcomes, with thresholds ≥ 0.52 demonstrating high sensitivity and specificity. Similarly, automated MPI (AM + MPI) provided a time-efficient, operator-independent assessment of the right ventricular function, detecting elevated MPI values in GDM fetuses despite normal umbilical artery Doppler findings [13,14,15,16].
3.3. Tissue Doppler Imaging (TDI)
Two studies employing tissue Doppler imaging (TDI) reported reduced E/E′ ratios, elevated LVMPI, and increased interventricular mechanical delay index (IVMDI) in GDM pregnancies, suggesting early diastolic dysfunction and mechanical dyssynchrony, with some indices (e.g., IVMDI ≥ 6.5 ms) being strongly predictive of adverse neonatal outcomes [17,18].
3.4. Speckle-Tracking Echocardiography (STE)
Advanced studies using speckle-tracking echocardiography (STE) demonstrated reduced atrial strain, impaired diastolic strain rates, and increased left ventricular torsion in the fetuses of diabetic mothers. These abnormalities were often present despite normal conventional Doppler findings, highlighting the superior sensitivity of STE in detecting subclinical myocardial dysfunction [19,20,21].
3.5. Dual-Gate Doppler
The dual-gate Doppler (DD) technique enabled the simultaneous acquisition of flow and myocardial velocity waveforms to improve temporal alignment, revealing bilateral ventricular diastolic dysfunction in the GDM fetuses and outperforming the conventional Doppler in sensitivity and reproducibility [22].
3.6. Aortic Isthmus Doppler
One study assessed aortic isthmus (AOI) flow using color and pulsed-wave Doppler, calculating the isthmus flow index (IFI) and the isthmus systolic index (ISI). Both indices were significantly reduced in the GDM fetuses, suggesting an early circulatory imbalance even when the peripheral Doppler indices remained normal [23].
3.7. Color Doppler and M-Mode
Color Doppler combined with M-mode echocardiography revealed an increased ventricular wall thickness and enhanced systolic indices (e.g., LVEF, LVFS) in the GDM-exposed fetuses. These findings support the presence of structural and functional adaptations in response to maternal hyperglycemia [24].
4. Discussion
4.1. Doppler Echocardiography—Traditional/Conventional Approach
The research conducted by Bogo et al. (2021) offers significant insights into the structural and functional cardiac modifications detected in the fetuses and neonates of mothers with gestational diabetes mellitus, despite clinically sufficient glycemic management. Doppler echocardiography, regarded as a conventional method, was employed to evaluate the myocardial thickness, myocardial performance index (MPI), and E/A ratios in the mitral and tricuspid valves during both the prenatal and postnatal periods. Hypertrophic cardiomyopathy (HPCM) was observed in 29% of the fetuses, but its incidence decreased to 6% after birth, indicating a temporary characteristic of cardiac hypertrophy. Nevertheless, functional metrics including the right and left ventricular MPI and the E/A ratios were markedly more affected during the neonatal period, suggesting that subclinical cardiac dysfunction may continue or possibly develop postnatally. The results endorse the integration of MPI and diastolic function indices as sensitive indicators in evaluating fetal heart health [13].
Similarly, an interesting study conducted by Bhorat et al. (2014) provides evidence that the fetuses of poorly managed GDM mothers demonstrate severe cardiac dysfunction, identifiable via conventional Doppler techniques. The authors demonstrated that elevated modified MPI (Mod-MPI) values and diminished mitral valve E/A ratios in the third trimester were significantly correlated with adverse perinatal outcomes, such as stillbirth, neonatal death, and NICU admission. A Mod-MPI threshold of ≥0.52 demonstrated a sensitivity of 100% and a specificity of 92% for predicting outcomes, highlighting its potential as a prognostic instrument in high-risk pregnancies. These findings underscore the diagnostic significance of functional Doppler indices in fetal surveillance and advocate for their incorporation into standard monitoring methods for pregnancies complicated by gestational diabetes mellitus [14].
In a study conducted by Pooransari et al. (2022), the embryonic cardiac function in pregnancies complicated by gestational and pregestational diabetes mellitus was examined using conventional pulsed-wave Doppler echocardiography. The study evaluated critical functional parameters, such as the left ventricular MPI, the isovolumic relaxation time (IVRT), and the E/A ratios in the mitral and tricuspid valves during the second and third trimesters. Structural measurements including interventricular septal thickness (IVST) and ventricular wall thickness (LVWT, RVWT) were assessed. The Hernandez-Andrade protocol was followed to acquire Doppler waveforms from a five-chamber view with meticulous alignment (<20° insonation angle) to capture the valve clicks for a more accurate MPI calculation. The results revealed that the diabetic group exhibited substantially elevated MPI and a prolonged IVRT, which suggests that both systolic and diastolic dysfunction were present. It is important to note that these abnormalities were observed in fetuses without myocardial hypertrophy and in mothers with excellent glycemic control, indicating that functional impairment may precede structural changes. The efficacy of standardized Doppler echocardiography as a sensitive instrument for the early detection of subclinical myocardial dysfunction in diabetic pregnancies was confirmed [15].
Considering Mod-MPI and MPI, the Mod-MPI is an adaptation of the original MPI, designed with the aim of improving the reproducibility and accuracy of fetal cardiac function assessments using Doppler ultrasound. Both are non-invasive, pulsed-wave Doppler-derived measures of global myocardial function. However, Mod-MPI utilizes the opening and closing of the mitral and aortic valves to define the isovolumetric contraction, ejection, and isovolumetric relaxation times, leading to better agreement and reduced variation compared to the original MPI [25,26,27]. The differences are summarized in Table 3.
Table 3.
Myocardial performance index (MPI) versus modified myocardial performance index (Mod-MPI).
4.2. Automated Right Ventricular MPI for Functional Assessment in Diabetic Pregnancies
Ding et al. (2024) examined the fetal right ventricular function during mid-to-late pregnancy utilizing automated myocardial performance index (AM+MPI) technology, contrasting the fetuses of diabetic and non-diabetic individuals. The tricuspid and pulmonary valves were recorded with synchronized inflow and outflow using color and pulsed-wave Doppler ultrasonography, respectively. The AM+MPI system minimizes operator variability by automatically identifying valve sounds to measure the isovolumic contraction time (ICT), isovolumic relaxation time (IRT), and ejection time (ET) within a normalized cardiac cycle. The right ventricular MPI was determined by dividing (ICT + IRT) by ET. The results of the study demonstrated that the MPI values of the fetuses of diabetic mothers were substantially higher than those of the controls (0.54 ± 0.05 vs. 0.48 ± 0.09, p < 0.05), suggesting that the general right ventricular function was impaired. It is important to note that this dysfunction was detectable in the absence of structural anomalies or aberrant umbilical artery Doppler findings. The study emphasizes the clinical utility of AM+MPI as a time-efficient, reproducible, and sensitive Doppler-based instrument for the detection of subclinical cardiac dysfunction in diabetic pregnancies [16].
4.3. Pulsed Tissue Doppler Imaging (TDI)
The study conducted by Hatém et al. (2008) offers a detailed evaluation of fetal diastolic function in pregnancies challenged by maternal diabetes using TDI. TDI is an advanced echocardiographic modality that enables the direct quantification of myocardial velocities throughout the cardiac cycle. The study was conducted on a total of 62 fetuses between 25 weeks gestation and term; the study compared the myocardial velocities at the mitral and tricuspid annuli among three groups: 13 fetuses of diabetic mothers with myocardial hypertrophy, 34 fetuses of diabetic mothers without myocardial hypertrophy, and 15 fetuses of mothers without diabetes. The TDI measurements were obtained from the apical four-chamber view, with sample volumes placed at the lateral mitral annulus, septal mitral annulus, and lateral tricuspid annulus. The parameters assessed included early (E′) and late (A′) diastolic myocardial velocities, systolic velocity (S′), and derived ratios such as E′/A′ and E/E′. The authors reported significantly elevated E′ and A′ velocities and reduced E/E′ ratios in the fetuses of diabetic mothers—regardless of the presence of septal hypertrophy—indicating impaired diastolic relaxation and altered ventricular compliance. The findings suggest the superior sensitivity of TDI over conventional pulsed-wave Doppler in detecting subclinical myocardial dysfunction and support its integration into fetal cardiac surveillance protocols for high-risk pregnancies such as those affected by GDM [17]. The TDI technique is used in fetal echocardiography to assess myocardial velocities and function as it provides valuable information about the heart’s systolic and diastolic performance, thus helping in the detection of potential abnormalities in fetal heart conditions. TDI is extremely useful in evaluating the myocardial motion and assessing diastolic function, which can be challenging to evaluate with conventional methods [28].
On the same note, Moghadam et al. (2024) implemented TDI to quantitatively evaluate the embryonic myocardial function and mechanical dyssynchrony in pregnancies that were complicated by overt maternal diabetes. TDI was conducted at 28 weeks gestation using an apical four-chamber view. Sample volumes were deposited at the lateral mitral annulus to derive the left ventricular myocardial performance index (LVMPI) and the early (Em) and late (Am) diastolic myocardial velocities. In addition, the temporal difference between the maximal systolic contractions of the right and left ventricles was measured to determine the interventricular mechanical delay index (IVMDI) using M-mode aligned across the interventricular septum. In comparison to the controls, the diabetic cohort exhibited substantially elevated Em, Am, LVMPI, and IVMDI values, which implies both mechanical dyssynchrony and diastolic dysfunction. It is important to note that IVMDI ≥ 6.5 ms and LVMPI ≥ 0.44 were highly predictive of adverse neonatal outcomes, with IVMDI achieving 100% specificity [18].
4.4. Doppler-Based Hemodynamic Assessment in GDM
Furthermore, Cai et al. (2024) contribute valuable insights into the vascular and structural cardiac adaptations in the fetuses of mothers with GDM, using conventional color Doppler ultrasound along with M-mode echocardiography. More precisely, the study assessed fetal hemodynamic parameters including the resistance index (RI), pulsatility index (PI), and systolic/diastolic ratio (S/D) in the middle cerebral artery (MCA), umbilical artery (UA), and renal artery (RA). These Doppler indices were significantly altered in the GDM group, reflecting a compensatory redistribution of fetal blood flow. In addition, M-mode echocardiography was employed for the evaluation of cardiac morphology and functionality, revealing an increased ventricular wall thickness and enhanced systolic function indices (e.g., LVEF, LVFS, RVFS) in those fetuses exposed to maternal hyperglycemia. Although the study did not utilize myocardial-specific Doppler techniques such as MPI or TDI, the broader utility of vascular Doppler surveillance in identifying subclinical cardiovascular stress in utero was emphasized. This supports the inclusion of arterial Doppler indices as complementary tools in the fetal assessment of GDM pregnancies [24]. Generally, M-mode echocardiography plays a pivotal role in fetal cardiac assessment by providing high-temporal-resolution imaging of the heart wall and valve motion, which is crucial for evaluating the fetal heart rate, rhythm, and myocardial contractility. It is especially valuable in detecting arrhythmias and assessing systolic function through measures like fractional shortening and tricuspid annular plane systolic excursion (TAPSE) [29,30].
4.5. Dual-Gate Doppler (DD)
The study of Hou et al. (2021) presents a comparative evaluation of fetal cardiac diastolic function in pregnancies complicated by GDM using both the conventional pulsed-wave Doppler and the emerging DD technique. The conventional Doppler assessment involved the sequential acquisition of mitral and tricuspid inflow velocities (E and A waves) and annular myocardial velocities (e′ and a′) using pulsed-wave Doppler and TDI, respectively. In contrast, the DD method enabled the simultaneous acquisition of both the flow and myocardial velocity waveforms within the same cardiac cycle by placing two independent sample volumes, one at the atrioventricular valve inflow and the other at the corresponding annulus. This approach minimized the beat-to-beat variability and improved the temporal alignment of the E/e′ ratio measurements. The study demonstrated that while both methods detected reduced E/e′ ratios in the fetuses of GDM mothers, the DD technique revealed statistically significant impairments in both the left and right ventricular diastolic function, whereas the conventional Doppler detected changes only in the right ventricle. The enhanced sensitivity and reproducibility of DD in detecting subclinical myocardial dysfunction supports its integration into fetal cardiac surveillance protocols for high-risk pregnancies [22].
4.6. Aortic Isthmus Doppler as an Uprising Marker of Fetal Cardiac Adaptation in GDM
Interestingly, Chen et al. (2024) employed color and pulsed-wave Doppler ultrasound to evaluate fetal aortic isthmus (AOI) hemodynamics in pregnancies complicated by GDM, offering an indirect yet physiologically meaningful assessment of fetal cardiac function. Doppler measurements included the systolic and diastolic flow velocity time integrals (S and D), the peak systolic velocity (PSV), and the systolic nadir (Ns), from which two derived indices were calculated: the isthmus flow index (IFI = (S + D)/S) and the isthmus systolic index (ISI = Ns/PSV). These indices reflect the balance of the left and right ventricular outputs and the relative vascular resistance between the cerebral and placental circulations. The study demonstrated significantly lower IFI and ISI values in the GDM group compared to the controls, suggesting early alterations in central fetal hemodynamics despite normal umbilical artery Doppler findings. Aortic isthmus Doppler can potentially be used as a sensitive adjunctive tool for detecting subclinical circulatory imbalances in GDM pregnancies, complementing the myocardial-specific Doppler techniques currently used in comprehensive fetal cardiac surveillance [23].
4.7. Integrated Doppler and Speckle-Tracking Assessment of Perinatal Cardiac Function in Diabetic Pregnancy
The study by Miranda et al. (2018) presented a thorough evaluation of fetal cardiac function in pregnancies complicated by maternal diabetes, employing both conventional Doppler echocardiography and a two-dimensional speckle-tracking analysis. A cohort of 129 fetuses at 30–33 weeks’ gestation was included. The researchers identified significant alterations in myocardial deformation in the diabetic group—specifically, impaired early and late diastolic strain rates in both ventricles and a reduced right ventricular global longitudinal strain (GLS)—despite the relatively preserved findings in the conventional echocardiographic parameters. These findings highlight the enhanced sensitivity of speckle-tracking in detecting subclinical functional impairment and suggest that standard Doppler indices may underestimate early cardiac dysfunction in gestational diabetes. The study supports the integration of advanced Doppler modalities, particularly speckle-tracking, into routine surveillance for high-risk pregnancies, reinforcing the objectives of this review to map and evaluate the diagnostic utility of various Doppler techniques in this context [21].
The study by Pathan et al. (2024) takes a closer look at how maternal diabetes, especially GDM, affects the developing fetal heart using cutting-edge speckle-tracking echocardiography (STE). By analyzing standard four-chamber ultrasound views, the researchers measured how the fetal left and right atria stretch and contract (strain), giving them a clearer depiction of early cardiac function. Interestingly, the fetuses exposed to maternal diabetes showed significantly lower left and right atrial strain, even though their overall heart size and function appeared normal using more traditional measures. These strain abnormalities appeared before changes in the GLS, suggesting that the atria might be more sensitive to subtle dysfunction in utero. STE reliably quantifies the intrinsic myocardial motion irrespective of the fetal position or insonation angle, making it particularly advantageous for detailed functional assessments. This study adds to the growing evidence that atrial strain could be an early marker of subclinical cardiac stress in high-risk pregnancies, and positions STE as a meaningful addition to fetal cardiac surveillance in GDM [19].
Moreover, Patey et al. (2019) conducted a prospective longitudinal study evaluating fetal and neonatal cardiac geometry and function in pregnancies affected by GDM and pre-GDM. The study employed a comprehensive echocardiographic protocol, including pulsed-wave Doppler, tissue Doppler imaging, and two-dimensional speckle-tracking echocardiography, to evaluate myocardial performance in utero and during the immediate postnatal period. Key Doppler-derived indices included the myocardial performance index (MPI′), isovolumetric contraction and relaxation times (IVCT′, IVRT′), and the E′/A′ and E/E′ ratios at the mitral, tricuspid, and septal annuli. Speckle-tracking was used to quantify the longitudinal, circumferential, and radial strain and strain rates, as well as the left ventricular torsion. Compared to controls, the fetuses and neonates of diabetic mothers exhibited altered ventricular geometry, increased wall thickness, elevated MPI′, and impaired diastolic function, with some abnormalities persisting postnatally. Notably, the LV torsion and basal radial strain rate were significantly elevated, suggesting compensatory mechanisms in response to altered loading conditions [20].
4.8. Strategy for Optimal Timing and Technique Selection in Fetal Cardiac Assessment of GDM Pregnancies
Based on the results of this scoping review of the available evidence, the following tiered strategy could be proposed to ensure optimal timing and technique selection for fetal cardiac assessment in GDM pregnancies, as presented in Table 4. By using pulsed-wave Doppler at the mid-trimester anatomy scan, then adding TDI and STE as the pregnancy advances, clinicians can maximize the early detection and sensitivity of subclinical cardiac alterations in GDM. Advanced techniques (dual-gate Doppler and automated MPI) should be reserved for those centers with the requisite software and expertise to further refine the risk stratification.
Table 4.
Strategy for optimal timing and technique selection for fetal cardiac assessment in GDM pregnancies.
4.9. Limitations
Although this scoping review furnishes a comprehensive synthesis of Doppler-based fetal cardiac assessment in diabetic pregnancies, several caveats merit attention. First, heterogeneity in the study methodologies and in the diagnostic thresholds for gestational diabetes mellitus impeded direct comparisons across investigations. Second, most studies were observational and did not uniformly report key parameters such as maternal glycemic control or postnatal cardiac outcomes. Third, our restriction to English language publications and a limited set of databases may have led to the omission of relevant research. Finally, by design, this scoping review did not undertake a formal critical appraisal of study quality. Nevertheless, despite these limitations, the findings illuminate the emerging trends and identify critical gaps, thereby guiding future research efforts.
4.10. Future Directions
Future research should aim to prospectively validate a structured, tiered surveillance protocol for fetal cardiac assessment in GDM pregnancies. Ideally, this protocol begins with the conventional pulsed-wave Doppler at the mid-trimester anatomy scan (24–28 weeks) to quantify the E/A ratios, isovolumic contraction and relaxation times, and global MPI, all of which have been shown to unmask early diastolic dysfunction. In the early third trimester (28–32 weeks), tissue Doppler imaging should be added to measure the annular E′/A′ and E/E′ ratios and the interventricular mechanical delay, thereby detecting subclinical diastolic impairments that may not be apparent using the conventional Doppler alone. Finally, speckle-tracking echocardiography performed at 30–34 weeks can quantify the atrial and ventricular strain and diastolic strain rates, offering the greatest sensitivity for detecting subtle systolic and diastolic abnormalities. Where available, dual-gate Doppler to enable simultaneous flow and tissue velocity measurements, and automated MPI algorithms should be integrated to further reduce operator dependency and improve the temporal alignment of key indices.
In parallel, future studies should establish gestational age- and GDM-specific normative percentiles for pulsed-wave, tissue Doppler, speckle-tracking, and automated MPI parameters. Complementary research should evaluate the use of mid- to late-gestation umbilical cord NT-proBNP levels as a biochemical trigger for targeted fetal echocardiographic screening, refining risk stratification in poorly controlled GDM. Longitudinal cohorts that correlate the prenatal Doppler and strain indices with postnatal cardiac structure, function, and early childhood cardiovascular risk are also essential. Finally, cost-effectiveness analyses comparing standard obstetric care to this multimodal surveillance approach will guide implementation and inform future guideline recommendations, with the ultimate goal of improving cardiovascular outcomes in the offspring of women with GDM.
5. Conclusions
Doppler-based ultrasound techniques, including pulsed-wave Doppler, tissue Doppler imaging, speckle-tracking echocardiography, dual-gate Doppler, and automated myocardial performance index, reliably detect subclinical structural and functional cardiac alterations in fetuses exposed to gestational diabetes mellitus. These modalities reveal diastolic dysfunction, myocardial performance impairments, and early hemodynamic imbalances even in pregnancies with optimal glycemic control, underscoring their value for enhanced fetal surveillance. Implementing a tiered assessment strategy that progresses from the conventional Doppler at mid-trimester to advanced deformation and automated methods in the third trimester may improve risk stratification and guide timely interventions. The prospective validation of standardized protocols, establishment of GDM-specific normative ranges, and longitudinal correlations with postnatal cardiovascular outcomes are essential next steps to translate these findings into clinical practice.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/jcm14165622/s1, Table S1: PRISMA-ScR Table. Ref. [31] is cited in Supplementary Materials.
Author Contributions
Conceptualization, S.T. and I.K.; methodology, I.K.; software, S.T.; validation, A.M., E.K. and T.P.; formal analysis, S.T., I.K. and T.P.; investigation, S.T. and I.K.; resources, S.T. and I.K.; data curation, S.T. and I.K.; writing—original draft preparation, S.T. and I.K.; writing—review and editing, A.M., E.K. and T.P.; visualization, S.T. and I.K.; supervision, T.P.; project administration, A.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Choudhury, A.A.; Devi Rajeswari, V. Gestational diabetes mellitus—A metabolic and reproductive disorder. Biomed. Pharmacother. 2021, 143, 112183. [Google Scholar] [CrossRef] [Scilit]
- Panaitescu, A. Gestational Diabetes. Obstetrical Perspective. Acta Endocrinol. 2016, 12, 331–334. [Google Scholar] [CrossRef] [Scilit]
- Ta, S. Diagnosis and Classification of Diabetes Mellitus. Diabetes Care 2014, 37 (Suppl. S1), S81–S90. [Google Scholar] [CrossRef] [Scilit]
- Mao, Y.; Hu, W.; Xia, B.; Liu, L.; Han, X.; Liu, Q. Association Between Gestational Diabetes Mellitus and the Risks of Type-Specific Cardiovascular Diseases. Front. Public Health 2022, 10, 940335. [Google Scholar] [CrossRef] [Scilit]
- Lee, S.M.; Shivakumar, M.; Park, J.W.; Jung, Y.M.; Choe, E.K.; Kwak, S.H.; Oh, S.; Park, J.S.; Jun, J.K.; Kim, D.; et al. Long-term cardiovascular outcomes of gestational diabetes mellitus: A prospective UK Biobank study. Cardiovasc. Diabetol. 2022, 21, 221. [Google Scholar] [CrossRef] [Scilit]
- Kramer, C.K.; Campbell, S.; Retnakaran, R. Gestational diabetes and the risk of cardiovascular disease in women: A systematic review and meta-analysis. Diabetologia 2019, 62, 905–914. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yu, Y.; Soohoo, M.; Sørensen, H.T.; Li, J.; Arah, O.A. Gestational Diabetes Mellitus and the Risks of Overall and Type-Specific Cardiovascular Diseases: A Population- and Sibling-Matched Cohort Study. Diabetes Care 2022, 45, 151–159. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Basu, M.; Garg, V. Maternal hyperglycemia and fetal cardiac development: Clinical impact and underlying mechanisms. Birth Defects Res. 2018, 110, 1504–1516. [Google Scholar] [CrossRef] [Scilit]
- Rodolaki, K.; Pergialiotis, V.; Iakovidou, N.; Boutsikou, T.; Iliodromiti, Z.; Kanaka-Gantenbein, C. The impact of maternal diabetes on the future health and neurodevelopment of the offspring: A review of the evidence. Front. Endocrinol. 2023, 14, 1125628. [Google Scholar] [CrossRef] [Scilit]
- Alnuaimi, S.A.; Jimaa, S.; Khandoker, A.H. Fetal Cardiac Doppler Signal Processing Techniques: Challenges and Future Research Directions. Front. Bioeng. Biotechnol. 2017, 5, 82. [Google Scholar] [CrossRef] [Scilit]
- Tutschek, B.; Schmidt, K. Sonographic Assessment of Fetal Cardiac Function: Indirect Measurements of Fetal Cardiac Function, Newer Techniques and Clinical Applications. Ultraschall Med. Eur. J. Ultrasound 2011, 33, E16–E24. [Google Scholar] [CrossRef] [Scilit]
- Tsokkou, S.; Konstantinidis, I.; Anastasiou, V.; Matsas, A.; Stamoula, E.; Peteinidou, E.; Sioga, A.; Papamitsou, T.; Ziakas, A.; Kamperidis, V. Fetal Supraventricular Tachycardia: What Do We Know up to This Day? J. Pers. Med. 2025, 15, 341. [Google Scholar] [CrossRef] [Scilit]
- Bogo, M.A.; Pabis, J.S.; Bonchoski, A.B.; Santos, D.C.D.; Pinto, T.J.; Simões, M.A.; Silva, J.C.; Pabis, F.C. Cardiomyopathy and cardiac function in fetuses and newborns of diabetic mothers. J. Pediatr. 2021, 97, 520–524. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bhorat, I.E.; Bagratee, J.S.; Pillay, M.; Reddy, T. Use of the myocardial performance index as a prognostic indicator of adverse fetal outcome in poorly controlled gestational diabetic pregnancies. Prenat. Diagn. 2014, 34, 1301–1306. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pooransari, P.; Mehrabi, S.; Mirzamoradi, M.; Salehgargari, S.; Afrakhteh, M. Comparison of Parameters of Fetal Doppler Echocardiography Between Mothers with and Without Diabetes. Int. J. Endocrinol. Metab. 2022, 20, e117524. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ding, Z.J.; Yue, J.Z.; Zhang, Y.D.; Yin, W. Research on evaluation of fetal right ventricular function in normal and diabetic pregnant women during mid to late pregnancy using automated MPI ultrasound detection technology. J. Matern. Fetal Neonatal Med. 2024, 37, 2424892. [Google Scholar] [CrossRef] [Scilit]
- Hatém, M.A.; Zielinsky, P.; Hatém, D.M.; Nicoloso, L.H.; Manica, J.L.; Piccoli Jr, A.L.; Zanettini, J.; Oliveira, V.; Scarpa, F.; Petracco, R. Assessment of diastolic ventricular function in fetuses of diabetic mothers using tissue Doppler. Cardiol. Young 2008, 18, 297–302. [Google Scholar] [CrossRef] [Scilit]
- Moghadam, M.K.; Hemmatian, M.N.; Mirmohammadkhani, M.; Rahmanian, M. Evaluation of Ventricular Dyssynchrony Measured by Tissue Doppler Indices in Fetuses of Diabetic Mothers: A Case-Control Study. J. Tehran Univ. Heart Cent. 2024, 19, 276–282. [Google Scholar] [CrossRef] [Scilit]
- Pathan, F.; Lam, P.; Sivapathan, S.; Pathan, S.; Gao, Z.; Orde, S.; Nirthanakumaran, D.; Negishi, K.; Nanan, R. Impact of maternal diabetes mellitus on fetal atrial strain. Int. J. Cardiovasc. Imaging 2024, 40, 1987–1994. [Google Scholar] [CrossRef] [Scilit]
- Patey, O.; Carvalho, J.S.; Thilaganathan, B. Perinatal changes in fetal cardiac geometry and function in diabetic pregnancy at term. Ultrasound Obstet. Gynecol. 2019, 54, 634–642. [Google Scholar] [CrossRef] [Scilit]
- Miranda, J.O.; Cerqueira, R.J.; Ramalho, C.; Areias, J.C.; Henriques-Coelho, T. Fetal Cardiac Function in Maternal Diabetes: A Conventional and Speckle-Tracking Echocardiographic Study. J. Am. Soc. Echocardiogr. 2018, 31, 333–341. [Google Scholar] [CrossRef] [Scilit]
- Hou, Q.; Yan, F.; Dong, X.; Liu, H.; Wu, J.; Li, J.; Ding, Y. Assessment of fetal cardiac diastolic function of gestational diabetes mellitus using dual-gate Doppler. Medicine 2021, 100, E26645. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, X.; Zhang, L.; Lu, J.; Shen, L. Assessing Fetal Circulatory Changes in Gestational Diabetes via Aortic Isthmus Doppler. Clin. Exp. Obstet. Gynecol. 2024, 51, 193. [Google Scholar] [CrossRef] [Scilit]
- Cai, D.; Yan, S. Ultrasonographic diagnosis of fetal hemodynamic parameters in pregnant women with diabetes mellitus in the third trimester of pregnancy. Heliyon 2024, 10, e30352. [Google Scholar] [CrossRef] [Scilit]
- Simsek, A. Modified Myocardial Performance Index in Fetal Growth Disturbances as Diagnostic and Prognostic Adjunct. Anatol. J. Cardiol. 2023, 27, 34–40. [Google Scholar] [CrossRef] [Scilit]
- Maheshwari, P.; Henry, A.; Welsh, A.W. The Fetal Modified Myocardial Performance Index: Is Automation the Future? Biomed. Res. Int. 2015, 2015, 215910. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hernandez-Andrade, E.; Figueroa-Diesel, H.; Kottman, C.; Illanes, S.; Arraztoa, J.; Acosta-Rojas, R.; Gratacos, E. Gestational-age-adjusted reference values for the modified myocardial performance index for evaluation of fetal left cardiac function. Ultrasound Obstet. Gynecol. 2007, 29, 321–325. [Google Scholar] [CrossRef] [Scilit]
- Paladini, D.; Lamberti, A.; Teodoro, A.; Arienzo, M.; Tartaglione, A.; Martinelli, P. Tissue Doppler imaging of the fetal heart. Ultrasound Obstet. Gynecol. 2000, 16, 530–535. [Google Scholar] [CrossRef] [Scilit]
- Moon-Grady, A.J.; Donofrio, M.T.; Gelehrter, S.; Hornberger, L.; Kreeger, J.; Lee, W.; Michelfelder, E.; Morris, S.A.; Peyvandi, S.; Pinto, N.M.; et al. Guidelines and Recommendations for Performance of the Fetal Echocardiogram: An Update from the American Society of Echocardiography. J. Am. Soc. Echocardiogr. 2023, 36, 679–723. [Google Scholar] [CrossRef] [Scilit]
- Wacker-Gussmann, A.; Strasburger, J.; Cuneo, B.; Wakai, R. Diagnosis and Treatment of Fetal Arrhythmia. Am. J. Perinatol. 2014, 31, 617–628. [Google Scholar] [CrossRef] [Scilit]
- Tricco, A.C.; Lillie, E.; Zarin, W.; O’Brien, K.K.; Colquhoun, H.; Levac, D.; Moher, D.; Peters, M.D.; Horsley, T.; Weeks, L.; et al. PRISMA Extension for Scoping Reviews (PRISMAScR): Checklist and Explanation. Ann Intern Med. 2018, 169, 467–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).