


Abstract
During rehabilitation, a large proportion of stroke patients either plateau or begin to lose motor skills. By priming the motor system, transcranial direct current stimulation (tDCS) is a promising clinical adjunct that could augment the gains acquired during therapy sessions. However, the extent to which patients show improvements following tDCS is highly variable. This variability may be due to heterogeneity in regions of cortical infarct, descending motor tract injury, and/or connectivity changes, all factors that require neuroimaging for precise quantification and that affect the actual amount and location of current delivery. If the relationship between these factors and tDCS efficacy were clarified, recovery from stroke using tDCS might be become more predictable. This review provides a comprehensive summary and timeline of the development of tDCS for stroke from the viewpoint of neuroimaging. Both animal and human studies that have explored detailed aspects of anatomy, connectivity, and brain activation dynamics relevant to tDCS are discussed. Selected computational works are also included to demonstrate how sophisticated strategies for reducing variable effects of tDCS, including electric field modeling, are moving the field ever closer towards the goal of personalizing tDCS for each individual. Finally, larger and more comprehensive randomized controlled trials involving tDCS for chronic stroke recovery are underway that likely will shed light on how specific tDCS parameters, such as dose, affect stroke outcomes. The success of these collective efforts will determine whether tDCS for chronic stroke gains regulatory approval and becomes clinical practice in the future.
1. Introduction
Transcranial direct current stimulation (tDCS) is a noninvasive form of neuromodulation that has shown promise in improving rates of motor recovery following stroke [1,2]. Numerous studies have suggested that the effectiveness of tDCS, particularly as an adjunct to rehabilitation, can even extend to the chronic phase of stroke recovery [1,3,4]. Notwithstanding, a major hurdle of the tDCS field is the high degree of intra- and inter-subject variability in outcomes when tDCS is used for stroke [2,3,4,5,6,7,8,9]. Currently, there remains widespread disagreement regarding the source of variable outcomes resulting from tDCS administration.
Advances in neuroimaging offer potentially fruitful benefits in overcoming this challenge. Individual patient neuroanatomy, connectivity, brain tissue architecture, hemodynamic signals, and neural physiological states can be quantified using commonly available neuroimaging sequences and analytic tools [5,6]. Moreover, many have questioned whether these functional and structural features could account for patient variability in tDCS outcomes and whether such variability relates directly to tDCS-induced motor recovery potential in chronic stroke patients [7].
The idea of using neuroimaging methods, such as fMRI, to elucidate biomarkers corresponding to tDCS response variability has been previously advanced [8]. If individual neuroimaging parameters were known and considered, response to tDCS could become more predictable, thereby reducing variability at scale and leading to broader acceptance (e.g., FDA approval) in the future. This paper reviews preclinical and clinical studies from 2000 to 2022 in which neuroimaging methods were used to investigate mechanisms of tDCS effect on chronic stroke recovery.
PubMed, Google Scholar, ScienceDirect, and Scopus were queried to conduct a comprehensive literature review with the following keywords, individually and in combination: “transcranial direct current stimulation”, “neuroimaging”, “MRI”, “magnetic resonance imaging”, and/or “stroke”. To meet criteria for inclusion in this review, published literature must have met the following requirements:
- Cortical activation via direct or peripheral stimulation in addition to neuroimaging must have been included in the animal studies.
- tDCS for chronic stroke survivors (defined as greater than or equal to six months from the time of stroke) in addition to neuroimaging must have been included in the human studies.
Combining tDCS with neuroimaging presents a novel methodological approach for unlocking functional correlates of tDCS mechanisms [10]. The studies outlined in this review (along with others currently ongoing) have the potential to determine the future of tDCS as a clinical treatment for the millions of individuals suffering from chronic stroke.
2. Preclinical Studies
In a 2001 report, Dijkhuizen and colleagues induced unilateral stroke in rodents and examined changes in cortical response to peripheral electrical stimulation (pES) [11]. Functional magnetic resonance imaging (fMRI) cortical activation patterns in a control (sham) group were primarily observed in the hemisphere contralateral to the stimulated forelimb, as expected. In contrast, in the stroke group, three days after infarct, pES-related activation was detected in the contralesional (ipsilateral) hemisphere in various non-motor-related areas (e.g., face, visual, hindlimbs, and barrel field regions of the primary somatosensory cortex). Fourteen days post-stroke, activation was prevalent in both hemispheres, suggesting a dynamic time course of compensatory and reorganizational changes in brain activation following stroke using pES.
In 2003, the same group investigated cortical hemodynamics and functional recovery using pES in the setting of transient focal ischemia (TFI) [12]. In this study, right middle cerebral artery (MCA) occlusion was performed for two hours in rodents followed by pES of the impaired (contralateral to the lesion) and unimpaired (ipsilateral to the lesion) limbs. The authors calculated a laterality index and demonstrated that, at 24 h and three days post-ischemia, contralesional activity was enhanced when the impaired limb was stimulated, similar to the group’s earlier results. At 14 days post-ischemia, perilesional cortical activity in the ipsilesional hemisphere once again predominated, indicating spatial and temporal dynamics of brain activation. Using neuroimaging, histology, behavioral measures, and neurological deficit scores, the authors were able to establish a direct relationship between cortical insult, degree of tissue injury, and motor recovery. The study concluded that the shift of activation to the contralesional hemisphere elevates as the necrotic burden increases. Although direct stimulation to the brain was not included, these two studies were important in establishing the time course and hemispheric activation changes induced by stroke in rodents.
Yoon et al. (2012) explored the effects of tDCS in relation to immunohistochemical and neuroimaging changes in the rodent brain [12]. Using an MCA TFI model, animals were randomly assigned to one of three stimulation groups: sham, early tDCS (stimulation one day after infarct), or late tDCS (stimulation five days after infarct). The timing of tDCS application was found to have no adverse effects on infarct ratio, volume, or edema index using MRI. However, levels of microtubule-associated protein 2 (MAP-2) and growth-associated protein 43 (GAP-43), both associated with neuroplasticity, differed depending on the timepoint of stimulation. The early tDCS group displayed significant MAP-2 expression, while the late tDCS group exhibited significant GAP-43 enhancement. Both early and late tDCS groups significantly improved in tasks assessing spatial memory, mobility, proprioception, and response to touch. The only group with additional improvement in balance ability was those who received late stimulation. Thus, potential benefits of tDCS on cellular mechanisms and timing of functional recovery have been better defined in this study.
Braun and colleagues (2016) used a neuronal tracer to perform positron emission tomography (PET) imaging in rodents with TFI to investigate how tDCS affects different cell populations within the central nervous system (CNS) [13]. Rodents were randomized to 10 days of tDCS for 15 min at 500μA with either cathodal or anodal polarity. The rodents in the sham group were sedated for 15 min without stimulation. They found that the subventricular zone (SVZ) ipsilateral to the occlusion had higher levels of neuroblast proliferation, suggestive of neurogenesis in response to the infarct. Anodal and cathodal tDCS were employed to address the authors’ secondary question regarding whether tDCS polarity affects different CNS cell types. While tDCS increased neuroblast density radiotracer uptake independent of polarity, oligodendrocytes, which form the myelin sheath, migrated toward the ischemic lesion following cathodal tDCS. In an upper- and lower-extremity motor task, anodal tDCS strengthened gait while cathodal tDCS enhanced both gait and limb strength. In summary, early animal studies revealed distinct activation patterns and cortical hemodynamic changes in response to tDCS. Moreover, these studies helped characterize the myriad cellular processes involved. These investigations established the foundation for using neuroimaging and noninvasive brain stimulation in acute rodent models (see Table 1).
Table 1.
Animal studies that incorporated tDCS and MRI.
3. Early Human Studies Using tDCS for Stroke
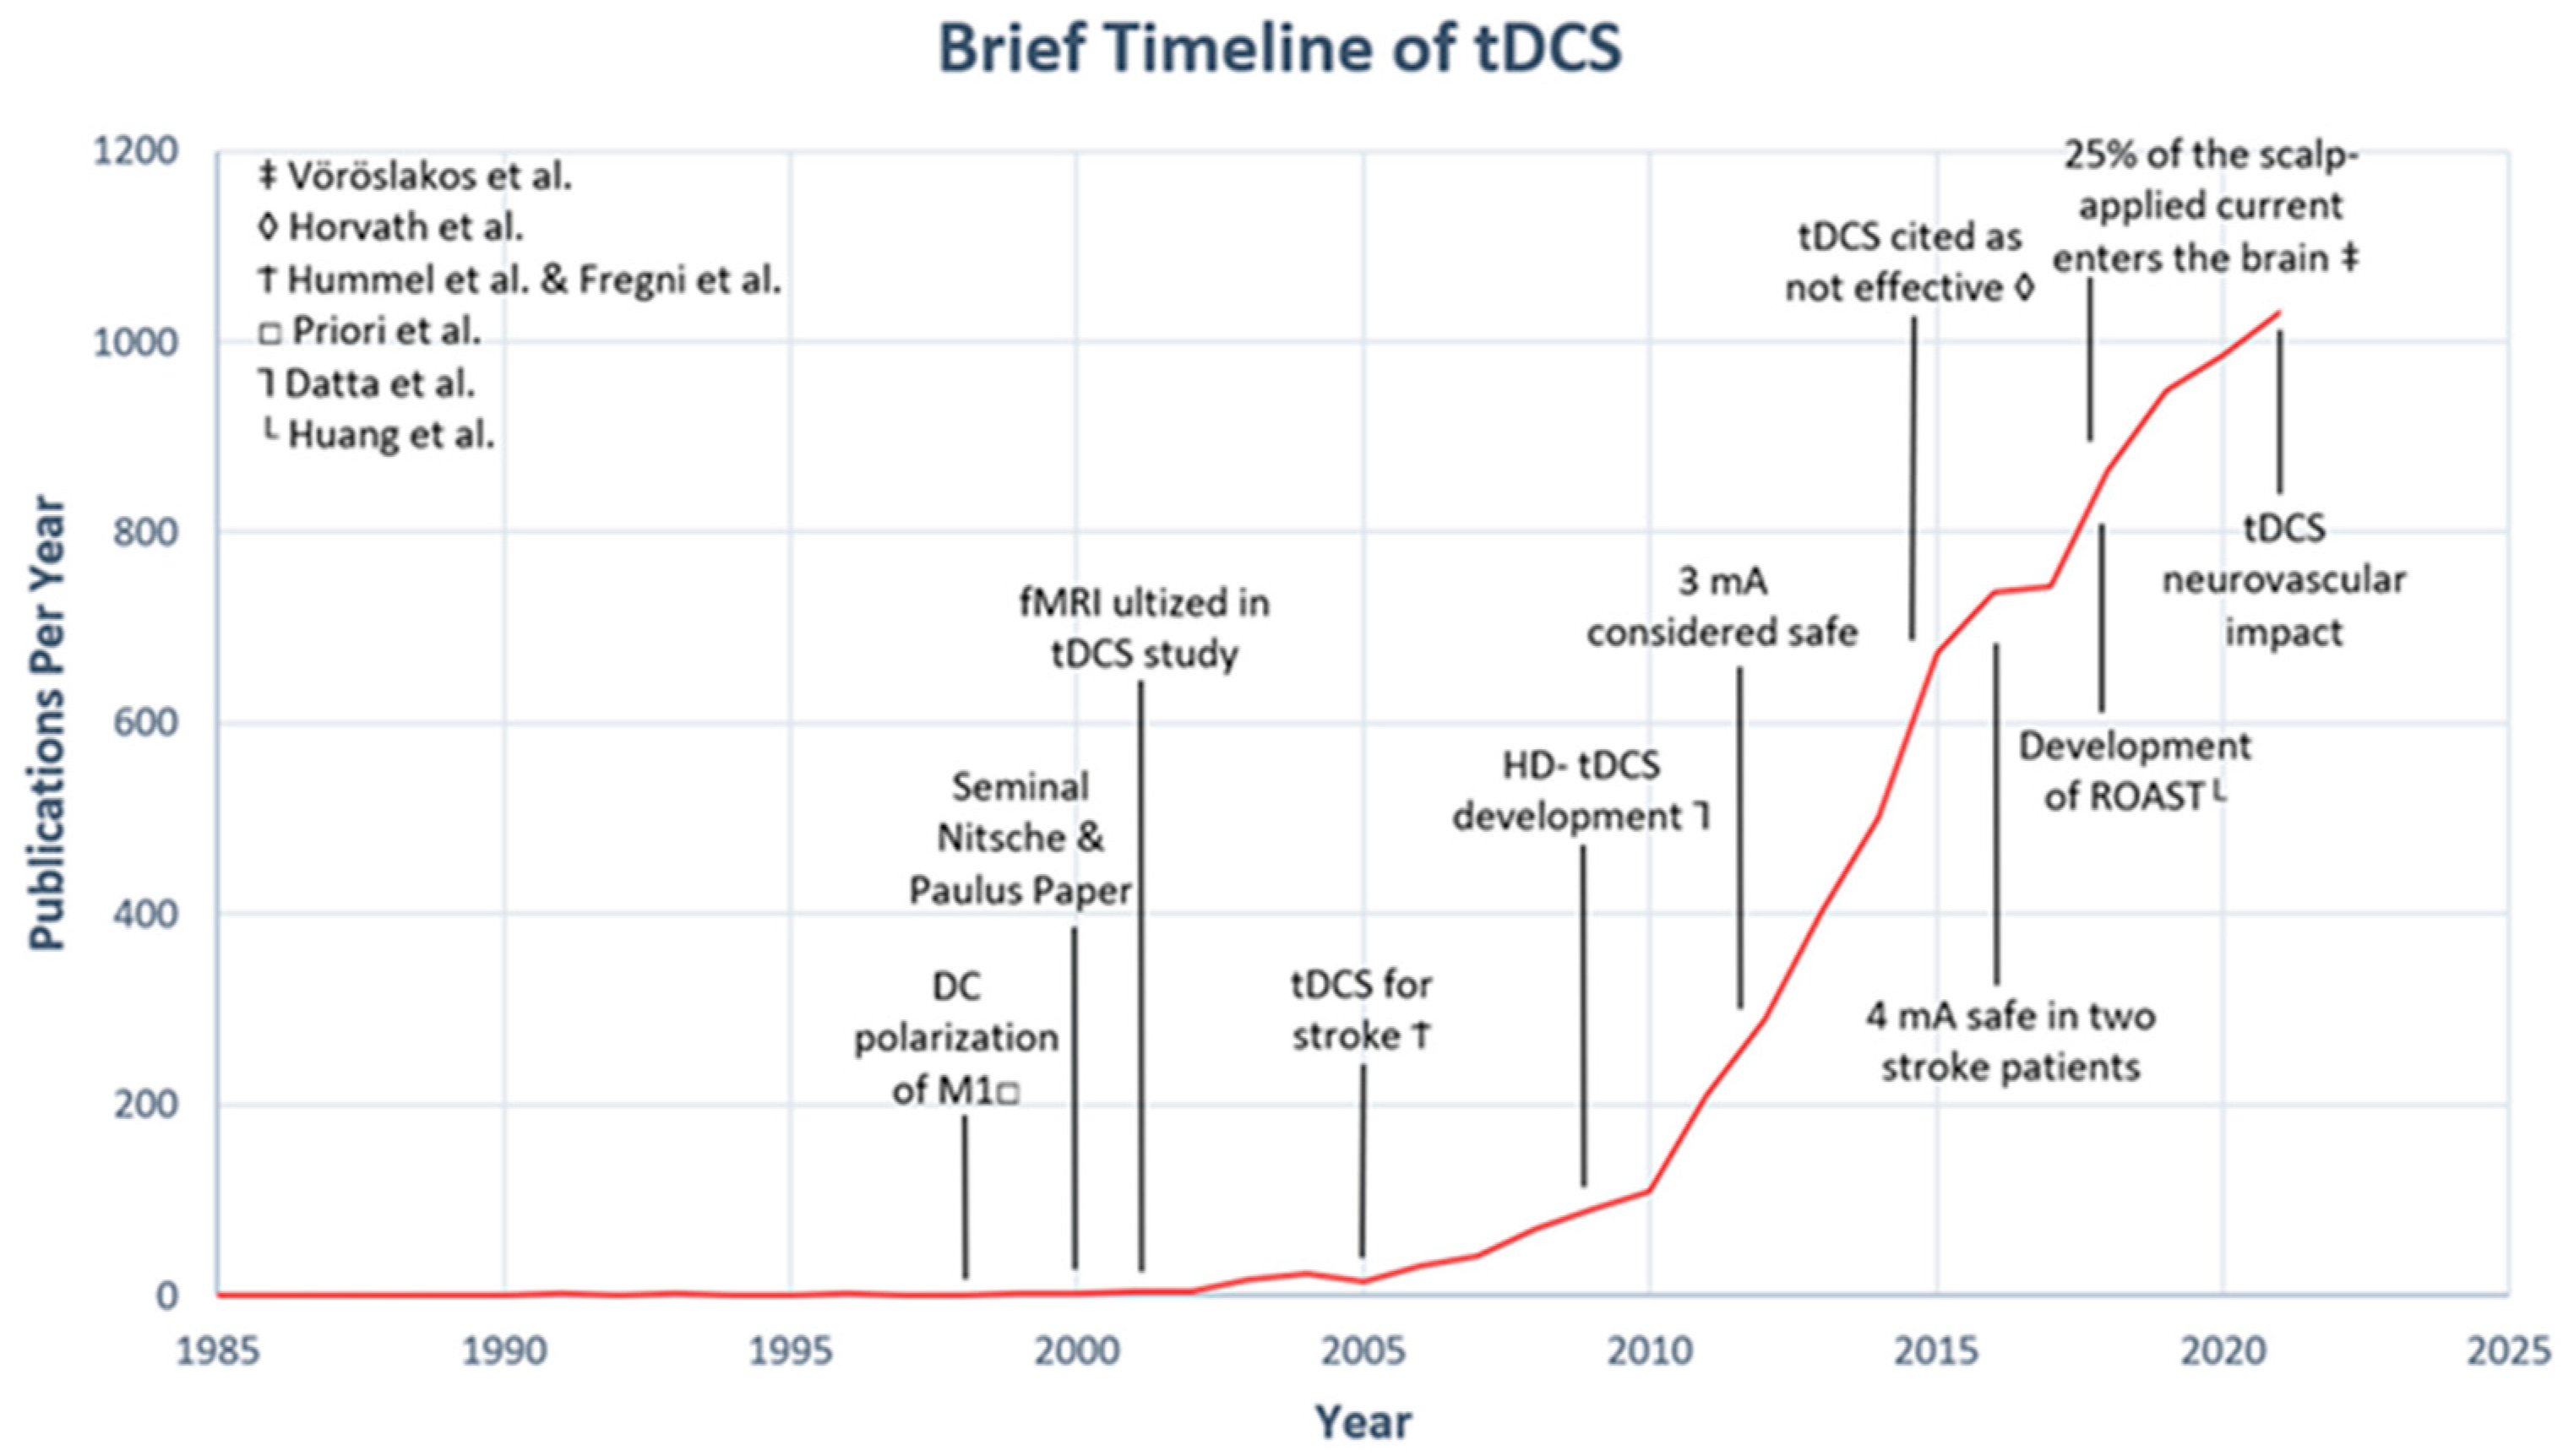
Many questions have been raised about the therapeutic impact and mechanism of action of tDCS since Nitsche and Paulus published their seminal paper describing the technique in 2000 [15]. In that study, Nitsche and Paulus examined the effects of low-intensity current stimulation applied to the scalp and observed that tDCS could induce sustained cortical excitability in the primary motor cortex of healthy controls for up to 90 min [14,15]. Immediately following this publication, many investigations ensued to understand whether tDCS could be used therapeutically for certain clinical populations (see Figure 1 for brief timeline). In 2005, two separate research groups administered tDCS to stroke survivors to address motor impairment [16,17,18]. Hummel et al. were the first to report motor improvement in a single patient with stroke following application of tDCS. In that study, anodal current (1 mA, 20 min) was delivered over the hand knob of the affected primary motor cortex while the cathode was placed supraorbitally on the contralateral scalp. Compared to sham stimulation, the patient demonstrated improvements in motor hand function as measured by the Jebsen–Taylor Hand Function Test (JTT) [18]. The findings reported by Hummel’s team were replicated when Fregni et al. (2005) investigated the effect of cathodal tDCS on the unaffected hemisphere in comparison to anodal tDCS to the affected hemisphere. In that study, six stroke survivors were randomly assigned to one of three groups using a crossover design: anodal tDCS of the affected hemisphere’s motor cortex, cathodal tDCS of the unaffected hemisphere’s motor cortex, or sham treatment. Fregni et al. observed that anodal stimulation of the affected hemisphere and cathodal stimulation of the unaffected hemisphere both significantly improved hand motor function. Fregni’s team extended their findings by demonstrating that cathodal tDCS can produce motor improvements comparable to anodal tDCS [17]. Interestingly, inter-subject variability emerged in the Fregni study. For example, one patient in the anodal tDCS group showed a 3.7% decline in hand function after tDCS, although no explanation was offered as to why this subject responded differently. Other investigators also began noting that tDCS was apparently only effective in some individuals with stroke, prompting many to wonder to what degree tDCS parameters should be optimized for a more consistent response [16,17,18] (see Table 2).
Figure 1.
Brief timeline of tDCS. The number of publications per year was calculated in PubMed using the following keyword search: “transcranial direct current stimulation” or “tDCS” [9,16,17,19,20,21,22].
Table 2.
Human studies that incorporated tDCS and MRI.
4. The Interhemispheric Inhibition Model Is Introduced Then Challenged
Fregni’s results represent an important development in the field in that they suggest that tDCS might aid stroke recovery by reducing transcallosal inhibition and thus restoring interhemispheric balance in patients recovering from stroke [47]. However, it was not clear whether the rebalancing of hemispheric excitability by tDCS directly facilitated improvements in the upper limbs. Stagg et al. (2012) addressed this question by investigating whether tDCS efficacy is contingent specifically on increased ipsilesional M1 activity [25]. Their study randomly assigned stroke patients to one of three treatment groups: anodal tDCS to the ipsilesional hemisphere; cathodal tDCS to the contralesional hemisphere; or sham. Once each day for three consecutive days, patients were scanned using fMRI while subjected to hand motor tasks. Patients received tDCS for 10 min at 1 mA before and after imaging. Importantly, anodal tDCS patients with larger task-related increases in ipsilesional M1 activation also had larger gains in motor improvement, while the cathodal group did not share this same relationship even though bilateral M1 activation was seen with cathodal tDCS.
To determine if stroke severity in either hemisphere is a predictor of tDCS effectiveness, Bradnam et al. (2012) adopted a multi-modal approach [23]. In twelve subjects, stroke severity was categorized depending on the extent of white matter tract damage as measured by diffusion tensor imaging (DTI). Subjects with varying upper extremity motor impairments were assessed along with white matter integrity scores based on fractional anisotropy (FA). The authors found that the integrity of white matter tracts is necessary for tDCS to successfully re-establish hemispheric balance. The same year, Lindenberg and colleagues (2012) reported that post-stroke patients’ white matter integrity of the corticospinal tract (CST), also measured by DTI, can predict the recovery of upper extremity motor function in stroke patients [24]. Both works corroborated earlier studies showing that white matter integrity plays a role in facilitating downstream effects of motor recovery, leading to increased use of neuroimaging and tractography in tDCS protocols [24].
Zheng conducted a pilot study in 2015 to further investigate the relationship between integrity of descending motor fibers such as the cortico–rubral–spinal and cortico–tegmental–spinal tracts and post-stroke motor impairment [31,48]. Ten patients received tDCS along with physical and occupational therapy for ten consecutive days. Ten additional patients did not receive either treatment (sham). Zheng found that chronic stroke survivors who participated in the treatment group (tDCS + PT/OT) showed a significant increase in upper extremity Fugl-Meyer Assessment (FMA) scores as opposed to the untreated group. Furthermore, FA values in the treatment group for ipsilesional descending motor fibers increased significantly. Zheng’s results imply that, if properly applied, tDCS could be used to modulate fiber connectivity and FA values.
In 2019, Lee and colleagues used tDCS and repetitive transcranial magnetic stimulation (rTMS) to investigate inter-individual variability among stroke survivors. They enrolled 21 subacute stroke patients who received simultaneous low-frequency rTMS on the contralesional M1 and anodal tDCS on the ipsilesional M1 daily for two weeks. Age-matched healthy controls were also enrolled. fMRI was performed both before and two months after rTMS and tDCS. Laterality indices and lesion maps were analyzed to quantify interhemispheric connectivity. They demonstrated that interhemispheric connectivity was significantly restored after tDCS and rTMS, lending credence to Bradnam’s work [23]. Participants who responded more favorably to tDCS, quantified by higher scores on the FMA-UE, also exhibited a greater interhemispheric balance.
Notwithstanding, many authors have challenged the role that interhemispheric rebalancing plays in motor recovery from stroke. For example, Stinear and colleagues (2015) used TMS to study corticomotor excitability in subacute stroke survivors and observed that interhemispheric inhibition was stable over time even though ipsilesional activity increased along with motor improvement [49]. The authors speculated that transcallosal inhibition was potentially preserved because the sample contained patients with intact motor cortices. Nevertheless, the concept of establishing an interhemispheric rebalance for motor recovery has been repeatedly questioned. McCambridge et al. (2018) studied modulation of contralesional excitability in ten chronic stroke survivors using tDCS. The authors found that anodal tDCS increased contralesional excitability while cathodal tDCS had no effect. Interestingly, magnetic resonance spectroscopy demonstrated changes in GABA concentration following tDCS, though motor function did not significantly improve with either polarity [50]. Thus, the role of transcallosal effects in motor recovery following stroke as it relates to tDCS remains an open debate [51].
5. Inter-Subject Variability: Methodological or Biological?
In the studies highlighted in previous sections, paradoxical outcomes in tDCS for stroke were attributed to high inter-subject variability, a phenomenon that has also been noted in tDCS for aphasia [51,52]. Potential factors contributing to response variability have been explored separately in numerous studies: demographics [53]; brain state before, during and after stimulation [54]; pharmacological agents [55], and unique individual neuroanatomy and physiological considerations [56]. To address these criticisms, many experts in the field have concluded that tDCS delivery may require individualized parameters, although how those parameters are computed and what biomarkers, if any, exist to support this approach are still controversial.
An emerging idea gaining traction is to personalize tDCS dosage using reverse-calculated electric field modeling [57,58,59,60]. The idea stems from the observation that uniform dosing methods, e.g., 2 mA, may underdose some individuals with larger scalp-to-cortex distance or increased cerebrospinal fluid volume, limiting therapeutic response [60,61,62]. These anatomical features may even be exacerbated in stroke given the presence of cortical damage [62], making post-stroke motor rehabilitation an ideal candidate for prospective reverse-calculation dosing for each patient.
The first step in reverse-calculation dosing involves determining an individualized, anatomically accurate tDCS electric field model based on each patient’s T1-weighted (T1w) structural MRI scan [63]. The brain is then segmented, which allows determination of current dispersion based on anatomical characteristics such as skin, cerebrospinal fluid (CSF), skull thickness, and grey and white matter. This processing pipeline helps to create an individualized volumetric finite element model needed for electric field modeling. Using this method, Caulfield and colleagues demonstrated that reverse-calculation modeling can produce the same group average electric field as occurs with uniform 2 mA dosing, while reducing between-individual electric field variance by over 100-fold [26].
Caulfield and colleagues subsequently derived a method in which transcranial electrical stimulation (TES) motor threshold (MT) can be used instead of MRI to estimate tDCS dosage based on reverse-calculation modeling [57]. In that study (2020), they utilized transcranial magnetic stimulation (TMS) to determine the MT hotspot. The anodal tDCS electrode was then placed over the MT hotspot, and the cathodal electrode was placed over the deltoid muscle. Based on how much stimulation reached the cortex, the investigators reverse calculated how much to adjust the scalp stimulation dosage to produce the desired electric field at the cortical target [57].
Two key issues remain with personalized dosing. First, the relationship between higher electric field (EF) magnitudes and therapeutic gains is still unclear, as most studies still report maximum dosage delivered instead of dose received. Second, as determined by structural MRI and computer modeling, the conductivity of various head and neck tissues, including skin, bone, and CSF, has a wide functional range. Thus, it is uncertain whether the dosages calculated from computational models will exceed the tolerable limits of current density to the scalp to achieve therapeutically beneficial EFs across the entire stroke population. To address whether tDCS EF normalization could be carried out by instead personalizing the montage used in each subject, Dmochoswki et al. (2013) used high-definition tDCS and MRI to define a target and optimize tDCS electrode configuration. The investigators created a volume conduction model for each patient to determine the electrode montage that would maximize the magnitude of the electric field. Using this approach, they significantly increased the electric field strength by 63%, although a behavioral measurement was not included in that study [26]. Currently, efforts at personalizing tDCS dose are still at an early but promising stage. If computational modeling could help resolve questions about individualizing electric field strength, then this approach might ultimately incorporate neuroimaging as a regular component of tDCS planning and implementation [64].
6. Randomized Control Trials (RCTs) for tDCS and Stroke Motor Recovery Are Still Evolving
Several Cochrane Reviews investigating the efficacy of tDCS for chronic stroke have been published. In a 2016 report, Elsner et al. analyzed 32 studies involving a total of 748 stroke survivors. The authors found low-to-moderate improvements in activities of daily living in stroke survivors such as holding utensils or picking up a cup following tDCS. In an updated Cochrane Review in 2020, evidence of low-to-moderate efficacy for tDCS therapy was again noted. The authors suggested that future large-scale randomized controlled trials for tDCS were needed to advance the field [24]. Subsequently, in 2021, the Cochrane Review upgraded its findings slightly to conclude that tDCS moderately enhanced outcomes in stroke survivors’ activities of daily living [31]. The updated review indicates the emergence of new evidence regarding use of tDCS in long-term stroke survivors, and in particular, improvements in selective attention [65], visuospatial working memory [65], planning [65], language abilities [66,67,68], faster acquisition of motor skills [68], and gait [69]. Nevertheless, the authors speculated that the inconsistency of tDCS still present in many studies stemmed from the lack of standardization across studies in dosage, voltage, current, stroke volume, and stimulation parameters. The inconsistent parameter settings across studies make it difficult to identify which factors are most associated with the efficacy of tDCS as a therapeutic tool.
Table 3 lists RCTs with experimental designs that included tDCS for chronic (except for two studies) stroke survivors and neuroimaging. In a randomized, double-blind RCT, Lefebvre and colleagues (2015) recruited nineteen stroke patients and conducted a crossover experimental design: (1) an intervention session where either sham or 1 mA of dual-tDCS (electrodes placed over both M1 regions) were applied during motor learning as measured by the Purdue Pegboard Test; (2) an imaging session one week later in which the subjects were asked to perform the motor skill that was learned in the first session to assess retention ability [70]. The investigators found that dual-tDCS did not improve speed but did significantly enhance the degree of motor skill learning and dexterity of the paretic arm [70]. Sham stimulation resulted in a decrease in Purdue Pegboard Test scores; interestingly, fMRI showed more widespread BOLD activation in the ipsilesional hemisphere after sham than after dual-tDCS [70]. Thus, dual-tDCS-induced fMRI activation is more focal compared to the sham group, suggesting that tDCS shapes the focality of cortical response during a specific task and is important for neuroplastic response distribution in the affected hemisphere.
Table 3.
Randomized Controlled Trails that incorporated tDCS and MRI.
In a subsequent study, Darkow and colleagues (2017) recruited sixteen stroke patients with aphasia and asked them to name pictures of common objects during fMRI acquisition. Anodal or sham tDCS was then administered to the ipsilesional M1. They observed that M1 stimulation had no effect on the motor network during a linguistic task, reinforcing the idea that the effects of stimulation are task-dependent and likely driven by task-specific networks rather than a single stimulation site [71].
Fortunately, the trend in reporting larger RCT results has continued to increase in recent years. At the time of the writing of this review, according to ClinicalTrials.gov, there are over 280 clinical trials involving tDCS for stroke, 40 of which are currently recruiting specifically for tDCS for motor recovery. Among these is a large Phase II study (ClinicalTrials.gov Identifier: NCT03826030–TRANSPORT 2) being carried out at 12 centers in the US, led by investigators at Duke University. The aim of TRANSPORT 2 is to expand work by Khadka, who reported that tDCS dosing as high as 4 mA is safe and well tolerated by stroke patients in the subacute to chronic phase [78]. TRANSPORT 2 randomizes 129 patients to sham, 2 mA and 4 mA tDCS along with motor assessments, MRI and TMS measurements. With such a large cohort and variety of possible structural defects, it will be important for the study to delineate whether response to escalating tDCS doses is contingent on the integrity of the CST and other important connections, as suggested by earlier studies. Another study, the VERIFY trial (ClinicalTrials.gov Identifier: NCT05338697) will use motor-evoked potential responses to TMS and neuroimaging metrics to validate a predictive tool for upper extremity motor outcomes.
Although tDCS is generally considered safe, it can result in mild side effects, including burning sensations, tingling, and numbness under the electrodes. While these effects are usually temporary, serious side effects, such as skin irritation, headache, fatigue, and dizziness, can occur in rare cases. Therefore, tDCS should only be administered by trained professionals in a controlled environment, and caution should be exercised in individuals with certain medical conditions or taking specific medications.
7. Discussion
As use of tDCS for stroke has evolved, the mechanisms underlying improvement in recovery are still highly debated within the tDCS community. Investigators continue to theorize how optimizing stimulation parameters might render outcomes more consistent. A standardized evaluation protocol is needed for authors and reviewers to assess the impact of features that may influence tDCS response variability. The tDCS community should collaborate to outline key features, including individual differences in brain anatomy, cortical excitability, and stimulation type and duration. A standardized evaluation protocol would enable investigators to compare and interpret the results of tDCS studies more effectively.
Initially, efforts to standardize were focused on the duration of effect, polarity and concerns regarding which stimulated hemisphere produced the strongest effect. As it became clear that establishing hemispheric balance and integrity of white matter tracts were not the only factors important for recovery, attention shifted to understanding the important role that task conditions and functional networks play in determining overall motor effect. Notwithstanding, all of these studies have suffered from some degree of variable effects, and it is now paramount that the tDCS scientific community address how to reduce variable outcomes if the technique is to gain clinical relevance. Increasingly, studies are incorporating neuroimaging in the experimental design in order to better understand these factors. This trend in the use of neuroimaging has the advantage of being complementary to multiple strategies for tDCS delivery, including electric field modeling, dose escalation and many others.
8. New and Unanswered Questions
As mentioned previously, Darkow demonstrated that brain activation following tDCS relies both on the stimulation site and the task performed [71]. Whether targeted brain network activation requires more than just reverse EF modeling or creating montages specific to individual patients remains unknown, but trialing these approaches on a larger scale in the future should be a priority. It is also reasonable to presume that tasks need to be tailored to the network activated. Neuroimaging should be considered essential in all of these experimental design types. Additionally, quantifying the actual tDCS current amplitude delivered to the cortex remains imperative as researchers look for the most precise method to determine the tailored therapeutic dose, as in Caulfield (2020) [58], or the maximum safest dose (2 vs. 4 mA), as in Chhatbar (2017) [79]. Moreover, in the last few years, groups have successfully challenged the conjecture proposed by Nitsche and Paulus in 2001 that tDCS after-effects only last up to 90 min [80]. Lefebvre demonstrated in 2015 that brain activation changes last for up to one week post-dual-tDCS. Those findings were replicated in 2017 [30,72,81]. Thus, the duration and number of administrations of tDCS are also critical considerations, particularly given the portability of the technique which allow it to be delivered both during rehabilitation and at home.
9. Future Considerations in Neuroimaging
Stroke can damage descending motor fiber tracts such as the CST [81,82,83], which is a crucial anatomical substrate for voluntary motor function. Efficacy of tDCS is dependent on an intact CST, including as it traverses through the internal capsule, to facilitate functional recovery; therefore, measuring CST structural damage in stroke is important [81,82,83]. In post-stroke patients, the FA of the CST is predictive of upper extremity motor recovery [83]. Higher FA values suggest more myelinated axons and alignment of fibers. As discussed in this review, DTI-based measures of the CST, specifically FA and mean diffusivity (MD), are commonly reported in stroke motor recovery studies [81,82,83]. However, a third measure of interest, mean kurtosis (MK), can also be obtained using diffusion kurtosis imaging (DKI); it quantifies the non-Gaussian quality of water diffusion [29]. DKI is a useful probe of microstructure and is sensitive to detecting changes in permeability [83,84,85]. MK data from acute ischemic stroke survivors revealed abnormalities adjacent to the infarct that were not present in other MR imaging sequences, including DTI, indicating MK’s potential utility in guiding tDCS targeting within stroke populations [85,86]. In the future, studies may consider incorporating advanced imaging metrics such as MK in experimental designs to ascertain if these represent additional biomarkers useful in tailoring tDCS approaches.
10. Limitations
This study is not devoid of limitations. One major challenge in understanding the heterogeneity of tDCS studies lies in the significant differences among patient cohorts and stimulation parameters. To address this issue, we recommend that future tDCS investigations prioritize the integration of neuroimaging techniques during concurrent stimulation. This approach can identify differences in neural networks and connectivity across samples, shedding light on tDCS response variability. Moreover, while direct current stimulation studies utilizing imaging techniques in preclinical stroke models are presently more limited in comparison to peripheral electrical stimulation, they are crucial to fully comprehend the underlying mechanisms of action and the potential clinical benefits of this technique. Such studies would allow for the identification of optimal target regions and stimulation protocols, potentially leading to improved stroke recovery outcomes. Hence, the continued investigation of direct current stimulation in preclinical stroke models using imaging techniques is imperative to advance our understanding of this technique and its therapeutic potential. Furthermore, when designing and executing studies involving tDCS, it is imperative to consider the side effects and contraindications associated with this intervention. While this review does not encompass such specifics, they warrant careful attention in all tDCS-related research endeavors.
Author Contributions
Conceptualization, C.A.S. and N.C.R.; writing—original draft preparation, C.A.S. and N.C.R.; writing—review and editing, C.A.S., N.C.R., W.F., L.B., S.K., J.H.J. and M.S.G. All authors have read and agreed to the published version of the manuscript.
Funding
Center of Biomedical Research Excellence (COBRE) in Stroke Recovery—Junior Investigator Research Project. Source: National Institutes of Health (5 P20 GM109040).
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
No new data were created or analyzed in this study. Data sharing is not applicable to this article.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Feng, W.; Kautz, S.A.; Schlaug, G.; Meinzer, C.; George, M.S.; Chhatbar, P.Y. Transcranial Direct Current Stimulation for Poststroke Motor Recovery: Challenges and Opportunities. PMR 2018, 10, S157–S164. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rudroff, T.; Workman, C.D.; Fietsam, A.C.; Kamholz, J. Response Variability in Transcranial Direct Current Stimulation: Why Sex Matters. Front. Psychiatry 2020, 11, 585. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- López-Alonso, V.; Fernández-Del-Olmo, M.; Costantini, A.; Gonzalez-Henriquez, J.J.; Cheeran, B. Intra-individual variability in the response to anodal transcranial direct current stimulation. Clin. Neurophysiol. 2015, 126, 2342–2347. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chew, T.; Ho, K.-A.; Loo, C.K. Inter- and Intra-individual Variability in Response to Transcranial Direct Current Stimulation (tDCS) at Varying Current Intensities. Brain Stimul. 2015, 8, 1130–1137. [Google Scholar] [CrossRef] [Scilit]
- Li, L.M.; Uehara, K.; Hanakawa, T. The contribution of interindividual factors to variability of response in transcranial direct current stimulation studies. Front. Cell. Neurosci. 2015, 9, 181. [Google Scholar] [CrossRef] [Scilit]
- López-Alonso, V.; Cheeran, B.; Río-Rodríguez, D.; Fernández-Del-Olmo, M. Inter-individual variability in response to non-invasive brain stimulation paradigms. Brain Stimul. 2014, 7, 372–380. [Google Scholar] [CrossRef] [Scilit]
- Wiethoff, S.; Hamada, M.; Rothwell, J.C. Variability in response to transcranial direct current stimulation of the motor cortex. Brain Stimul. 2014, 7, 468–475. [Google Scholar] [CrossRef] [Scilit]
- Krause, B.; Kadosh, R.C. Not all brains are created equal: The relevance of individual differences in responsiveness to transcranial electrical stimulation. Front. Syst. Neurosci. 2014, 8, 25. [Google Scholar] [CrossRef] [Scilit]
- Datta, A.; Truong, D.; Minhas, P.; Parra, L.C.; Bikson, M. Inter-Individual Variation during Transcranial Direct Current Stimulation and Normalization of Dose Using MRI-Derived Computational Models. Front. Psychiatry 2012, 3, 91. [Google Scholar] [CrossRef] [Scilit]
- Esmaeilpour, Z.; Shereen, A.D.; Ghobadi-Azbari, P.; Datta, A.; Woods, A.J.; Ironside, M.; O’Shea, J.; Kirk, U.; Bikson, M.; Ekhtiari, H. Methodology for tDCS integration with fMRI. Hum. Brain Mapp. 2020, 41, 1950–1967. [Google Scholar] [CrossRef] [Scilit]
- Dijkhuizen, R.M.; Ren, J.; Mandeville, J.B.; Wu, O.; Ozdag, F.M.; Moskowitz, M.A.; Rosen, B.R.; Finklestein, S.P. Functional magnetic resonance imaging of reorganization in rat brain after stroke. Proc. Natl. Acad. Sci. USA 2001, 98, 12766–12771. [Google Scholar] [CrossRef] [Scilit]
- Dijkhuizen, R.M.; Singhal, A.B.; Mandeville, J.B.; Wu, O.; Halpern, E.F.; Finklestein, S.P.; Rosen, B.R.; Lo, E.H. Correlation between brain reorganization, ischemic damage, and neurologic status after transient focal cerebral ischemia in rats: A functional magnetic resonance imaging study. J. Neurosci. 2003, 23, 510–517. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Braun, R.; Klein, R.; Walter, H.L.; Ohren, M.; Freudenmacher, L.; Getachew, K.; Ladwig, A.; Luelling, J.; Neumaier, B.; Endepols, H.; et al. Transcranial direct current stimulation accelerates recovery of function, induces neurogenesis and recruits oligodendrocyte precursors in a rat model of stroke. Exp. Neurol. 2016, 279, 127–136. [Google Scholar] [CrossRef] [Scilit]
- Yoon, K.J.; Oh, B.M.; Kim, D.Y. Functional improvement and neuroplastic effects of anodal transcranial direct current stimulation (tDCS) delivered 1 day vs. 1 week after cerebral ischemia in rats. Brain Res. 2012, 1452, 61–72. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nitsche, M.A.; Paulus, W. Sustained excitability elevations induced by transcranial DC motor cortex stimulation in humans. Neurology 2001, 57, 1899–1901. [Google Scholar] [CrossRef] [Scilit]
- Hummel, F.; Celnik, P.; Giraux, P.; Floel, A.; Wu, W.-H.; Gerloff, C.; Cohen, L.G. Effects of non-invasive cortical stimulation on skilled motor function in chronic stroke. Brain 2005, 128, 490–499. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fregni, F.; Boggio, P.S.; Mansur, C.G.; Wagner, T.; Ferreira, M.J.L.; Lima, M.C.; Rigonatti, S.P.; Marcolin, M.A.; Freedman, S.D.; Nitsche, M.A.; et al. Transcranial direct current stimulation of the unaffected hemisphere in stroke patients. Neuroreport 2005, 16, 1551–1555. [Google Scholar] [CrossRef] [Scilit]
- Hummel, F.; Cohen, L.G. Improvement of motor function with noninvasive cortical stimulation in a patient with chronic stroke. Neurorehabilit. Neural Repair 2005, 19, 14–19. [Google Scholar] [CrossRef] [Scilit]
- Vöröslakos, M.; Takeuchi, Y.; Brinyiczki, K.; Zombori, T.; Oliva, A.; Fernández-Ruiz, A.; Kozák, G.; Tamás Kincses, Z.; Iványi, B.; Buzsáki, G.; et al. Direct effects of transcranial electric stimulation on brain circuits in rats and humans. Nat Commun 2018, 9, 483. [Google Scholar] [CrossRef] [Scilit]
- Forte, J.D.; Carter, O. Evidence that transcranial direct current stimulation (tDCS) generates little-to-no reliable neurophysiologic effect beyond MEP amplitude modulation in healthy human subjects: A systematic review. Neuropsychologia 2015, 66, 213–236. [Google Scholar] [CrossRef] [Scilit]
- Priori, A. Brain polarization in humans: A reappraisal of an old tool for prolonged non-invasive modulation of brain excitability. Clin. Neurophysiol. 2003, 114, 589–595. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, Y.; Datta, A.; Bikson, M.; Parra, L.C. ROAST: An Open-Source, Fully-Automated, Realistic Volumetric-Approach-Based Simulator For TES. In Proceedings of the 2018 40th Annual International Conference of the IEEE Engineering in Medicine and Biology Society (EMBC), Honolulu, HI, USA, 18–21 July 2018; pp. 3072–3075. [Google Scholar] [CrossRef] [Scilit]
- Bradnam, L.V.; Stinear, C.M.; Barber, P.A.; Byblow, W.D. Contralesional hemisphere control of the proximal paretic upper limb following stroke. Cereb. Cortex 2012, 22, 2662–2671. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lindenberg, R.; Zhu, L.L.; Rüber, T.; Schlaug, G. Predicting functional motor potential in chronic stroke patients using diffusion tensor imaging. Hum. Brain Mapp. 2012, 33, 1040–1051. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stagg, C.J.; Bachtiar, V.; O’Shea, J.; Allman, C.; Bosnell, R.A.; Kischka, U.; Matthews, P.M.; Johansen-Berg, H. Cortical activation changes underlying stimulation-induced behavioural gains in chronic stroke. Brain 2012, 135, 276–284. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dmochowski, J.F.; Datta, A.; Huang, Y.; Richardson, J.D.; Bikson, M.; Fridriksson, J.; Parra, L.C. Targeted transcranial direct current stimulation for rehabilitation after stroke. Neuroimage 2013, 75, 12–19. [Google Scholar] [CrossRef] [Scilit]
- Gillick, B.T.; Kirton, A.; Carmel, J.B.; Minhas, P.; Bikson, M. Pediatric stroke and transcranial direct current stimulation: Methods for rational individualized dose optimization. Front. Hum. Neurosci. 2014, 8, 739. [Google Scholar] [CrossRef] [Scilit]
- Rosso, C.; Perlbarg, V.; Valabregue, R.; Arbizu, C.; Ferrieux, S.; Alshawan, B.; Vargas, P.; Leger, A.; Zavanone, C.; Corvol, J.; et al. Broca’s area damage is necessary but not sufficient to induce after-effects of cathodal tdcs on the unaffected hemisphere in post-stroke aphasia. Brain Stimul. 2014, 7, 627–635. [Google Scholar] [CrossRef] [Scilit]
- Jindal, U.; Sood, M.; Dutta, A.; Chowdhury, S.R. Development of Point of Care Testing Device for Neurovascular Coupling from Simultaneous Recording of EEG and NIRS During Anodal Transcranial Direct Current Stimulation. IEEE J. Transl. Eng. Health Med. 2015, 3, 2000112. [Google Scholar] [CrossRef] [Scilit]
- Lefebvre, S.; Dricot, L.; Laloux, P.; Gradkowski, W.; Desfontaines, P.; Evrard, F.; Peeters, A.; Jamart, J.; Vandermeeren, Y. Neural substrates underlying stimulation-enhanced motor skill learning after stroke. Brain 2015, 138, 149–163. [Google Scholar] [CrossRef] [Scilit]
- Zheng, X.; Schlaug, G. Structural white matter changes in descending motor tracts correlate with improvements in motor impairment after undergoing a treatment course of tDCS and physical therapy. Front. Hum. Neurosci. 2015, 9, 229. [Google Scholar] [CrossRef] [Scilit]
- Chen, J.L.; Schlaug, G. Increased resting state connectivity between ipsilesional motor cortex and contralesional premotor cortex after transcranial direct current stimulation with physical therapy. Sci. Rep. 2016, 6, 23271. [Google Scholar] [CrossRef] [Scilit]
- Sebastian, R.; Saxena, S.; Tsapkini, K.; Faria, A.V.; Long, C.; Wright, A.; Davis, C.; Tippett, D.C.; Mourdoukoutas, A.P.; Bikson, M.; et al. Cerebellar tDCS: A Novel Approach to Augment Language Treatment Post-stroke. Front. Hum. Neurosci. 2017, 10, 695. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hordacre, B.; Moezzi, B.; Ridding, M.C. Neuroplasticity and network connectivity of the motor cortex following stroke: A transcranial direct current stimulation study. Hum. Brain Mapp. 2018, 39, 3326–3339. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Larcombe, S.J.; Kulyomina, Y.; Antonova, N.; Ajina, S.; Stagg, C.J.; Clatworthy, P.L.; Bridge, H. Visual training in hemianopia alters neural activity in the absence of behavioural improvement: A pilot study. Ophthalmic Physiol. Opt. 2018, 38, 538–549. [Google Scholar] [CrossRef] [Scilit]
- Sánchez-Kuhn, A.; Medina, Y.; García-Pérez, M.; De Haro, P.; Flores, P.; Sánchez-Santed, F. Transcranial direct current stimulation treatment in chronic after-stroke dysphagia: A clinical case. Psicothema 2019, 31, 179–183. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iyer, P.C.; Rosenberg, A.; Baynard, T.; Madhavan, S. Influence of neurovascular mechanisms on response to tDCS: An exploratory study. Exp. Brain Res. 2019, 237, 2829–2840. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, J.; Lee, A.; Kim, H.; Shin, M.; Yun, S.M.; Jung, Y.; Chang, W.H.; Kim, Y.-H. Different Brain Connectivity between Responders and Nonresponders to Dual-Mode Noninvasive Brain Stimulation over Bilateral Primary Motor Cortices in Stroke Patients. Neural Plast. 2019, 2019, 3826495. [Google Scholar] [CrossRef] [Scilit]
- Abualait, T.S. Effects of transcranial direct current stimulation of primary motor cortex on cortical sensory deficits and hand dexterity in a patient with stroke: A case study. J. Int. Med. Res. 2020, 48, 300060519894137. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kuo, I.J.; Tang, C.W.; Tsai, Y.A.; Tang, S.C.; Lin, C.J.; Hsu, S.P.; Liang, W.K.; Juan, C.H.; Zich, C.; Stagg, C.J.; et al. Neurophysiological signatures of hand motor response to dual-transcranial direct current stimulation in subacute stroke: A TMS and MEG study. J. Neuroeng. Rehabil. 2020, 17, 72. [Google Scholar] [CrossRef] [Scilit]
- Richard, G.; Kolskår, K.; Ulrichsen, K.M.; Kaufmann, T.; Alnæs, D.; Sanders, A.-M.; Dørum, E.S.; Sánchez, J.M.; Petersen, A.; Ihle-Hansen, H.; et al. Brain age prediction in stroke patients: Highly reliable but limited sensitivity to cognitive performance and response to cognitive training. NeuroImage Clin. 2020, 25, 102159. [Google Scholar] [CrossRef] [Scilit]
- Rezaee, Z.; Ranjan, S.; Solanki, D.; Bhattacharya, M.; Srivastava, M.V.P.; Lahiri, U.; Dutta, A. Feasibility of combining functional near-infrared spectroscopy with electroencephalography to identify chronic stroke responders to cerebellar transcranial direct current stimulation—A computational modeling and portable neuroimaging methodological study. Cerebellum 2021, 20, 853–871. [Google Scholar] [CrossRef] [Scilit]
- Lee, G.; Lee, J.; Kim, J.; Kim, H.; Chang, W.H.; Kim, Y.-H. Whole Brain Hemodynamic Response Based on Synchrony Analysis of Brain Signals for Effective Application of HD-tDCS in Stroke Patients: An fNIRS Study. J. Pers. Med. 2022, 12, 432. [Google Scholar] [CrossRef] [Scilit]
- Kalloch, B.; Weise, K.; Lampe, L.; Bazin, P.-L.; Villringer, A.; Hlawitschka, M.; Sehm, B. The influence of white matter lesions on the electric field in transcranial electric stimulation. NeuroImage Clin. 2022, 35, 103071. [Google Scholar] [CrossRef] [Scilit]
- Hua, H.; Zhang, B.; Wang, X.; He, Y.; Lai, M.; Chen, N.; Liu, J. Diffusion Tensor Imaging Observation of Frontal Lobe Multidirectional Transcranial Direct Current Stimulation in Stroke Patients with Memory Impairment. J. Health Eng. 2022, 2022, 2545762. [Google Scholar] [CrossRef] [Scilit]
- Yuan, K.; Chen, C.; Lou, W.-T.; Khan, A.; Ti, E.C.-H.; Lau, C.C.-Y.; Wang, X.; Chu, W.C.-W.; Tong, R.K.-Y. Differential Effects of 10 and 20 Hz Brain Stimulation in Chronic Stroke: A tACS-fMRI Study. IEEE Trans. Neural Syst. Rehabil. Eng. 2022, 30, 455–464. [Google Scholar] [CrossRef] [Scilit]
- Morya, E.; Monte-Silva, K.; Bikson, M.; Esmaeilpour, Z.; Biazoli, C.E.; Fonseca, A.; Bocci, T.; Farzan, F.; Chatterjee, R.; Hausdorff, J.M.; et al. Beyond the target area: An integrative view of tDCS-induced motor cortex modulation in patients and athletes. J. Neuroeng. Rehabil. 2019, 16, 141. [Google Scholar] [CrossRef] [Scilit]
- Feng, W.; Wang, J.; Chhatbar, P.Y.; Doughty, C.; Landsittel, D.; Lioutas, V.-A.; Kautz, S.A.; Schlaug, G. Corticospinal tract lesion load: An imaging biomarker for stroke motor outcomes. Ann. Neurol. 2015, 78, 860–870. [Google Scholar] [CrossRef] [Scilit]
- Stinear, C.; Petoe, M.; Byblow, W.D. Primary Motor Cortex Excitability During Recovery After Stroke: Implications for Neuromodulation. Brain Stimul. 2015, 8, 1183–1190. [Google Scholar] [CrossRef] [Scilit]
- McCambridge, A.B.; Stinear, J.W.; Byblow, W.D. Revisiting interhemispheric imbalance in chronic stroke: A tDCS study. Clin. Neurophysiol. 2018, 129, 42–50. [Google Scholar] [CrossRef] [Scilit]
- Cunningham, D.A.; Machado, A.; Janini, D.; Varnerin, N.; Bonnett, C.; Yue, G.; Jones, S.; Lowe, M.; Beall, E.; Sakaie, K.; et al. Assessment of inter-hemispheric imbalance using imaging and noninvasive brain stimulation in patients with chronic stroke. Arch. Phys. Med. Rehabil. 2015, 96, S94–S103. [Google Scholar] [CrossRef] [Scilit]
- Guerra, A.; Lopez-Alonso, V.; Cheeran, B.; Suppa, A. Variability in non-invasive brain stimulation studies: Reasons and results. Neurosci. Lett. 2020, 719, 133330. [Google Scholar] [CrossRef] [Scilit]
- Pestalozzi, M.I.; Di Pietro, M.; Gaytanidis, C.M.; Spierer, L.; Schnider, A.; Chouiter, L.; Colombo, F.; Annoni, J.-M.; Jost, L.B. Effects of Prefrontal Transcranial Direct Current Stimulation on Lexical Access in Chronic Poststroke Aphasia. Neurorehabilit. Neural Repair 2018, 32, 913–923. [Google Scholar] [CrossRef] [Scilit]
- Hodics, T.; Cohen, L.G.; Pezzullo, J.C.; Kowalske, K.; Dromerick, A.W. Barriers to Enrollment in Post-Stroke Brain Stimulation in a Racially and Ethnically Diverse Population. Neurorehabilit. Neural Repair 2022, 36, 596–602. [Google Scholar] [CrossRef] [Scilit]
- Li, L.M.; Violante, I.R.; Leech, R.; Ross, E.; Hampshire, A.; Opitz, A.; Rothwell, J.C.; Carmichael, D.W.; Sharp, D.J. Brain state and polarity dependent modulation of brain networks by transcranial direct current stimulation. Hum. Brain Mapp. 2019, 40, 904–915. [Google Scholar] [CrossRef] [Scilit]
- Grazzi, L.; Usai, S.; Bolognini, N.; Grignani, E.; Sansone, E.; Tramacere, I.; Maravita, A.; Lauria, G. No efficacy of transcranial direct current stimulation on chronic migraine with medication overuse: A double blind, randomised clinical trial. Cephalalgia 2020, 40, 1202–1211. [Google Scholar] [CrossRef] [Scilit]
- Caulfield, K.A.; Badran, B.W.; DeVries, W.H.; Summers, P.M.; Kofmehl, E.; Li, X.; Borckardt, J.J.; Bikson, M.; George, M.S. Transcranial electrical stimulation motor threshold can estimate individualized tDCS dosage from reverse-calculation electric-field modeling. Brain Stimul. 2020, 13, 961–969. [Google Scholar] [CrossRef] [Scilit]
- Caulfield, K.A.; Badran, B.W.; Li, X.; Bikson, M.; George, M.S. Can transcranial electrical stimulation motor threshold estimate individualized tDCS doses over the prefrontal cortex? Evidence from reverse-calculation electric field modeling. Brain Stimul. 2020, 13, 1150–1152. [Google Scholar] [CrossRef] [Scilit]
- Evans, C.; Bachmann, C.; Lee, J.S.; Gregoriou, E.; Ward, N.; Bestmann, S. Dose-controlled tDCS reduces electric field intensity variability at a cortical target site. Brain Stimul. 2020, 13, 125–136. [Google Scholar] [CrossRef] [Scilit]
- Van Hoornweder, S.; Nuyts, M.; Frieske, J.; Verstraelen, S.; Meesen, R.L.J.; Caulfield, K.A. A Systematic Review and Large-Scale tES and TMS Electric Field Modeling Study Reveals How Outcome Measure Selection Alters Results in a Person- and Montage-Specific Manner. Preprint. bioRxiv 2023. [Google Scholar] [CrossRef] [Scilit]
- Laakso, I.; Tanaka, S.; Koyama, S.; De Santis, V.; Hirata, A. Inter-subject Variability in Electric Fields of Motor Cortical tDCS. Brain Stimul. 2015, 8, 906–913. [Google Scholar] [CrossRef] [Scilit]
- Zanto, T.F.; Jones, K.T.; Ostrand, A.E.; Hsu, W.Y.; Campusano, R.; Gazzaley, A. Individual differences in neuroanatomy and neurophysiology predict effects of transcranial alternating current stimulation. Brain Stimul. 2021, 14, 1317–1329. [Google Scholar] [CrossRef] [Scilit]
- Lefebvre, S.; Liew, S.-L. Anatomical Parameters of tDCS to Modulate the Motor System after Stroke: A Review. Front. Neurol. 2017, 8, 29. [Google Scholar] [CrossRef] [Scilit]
- Caulfield, K.A.; Indahlastari, A.; Nissim, N.R.; Bs, J.W.L.; Bs, H.H.F.; Woods, A.J.; George, M.S. Electric Field Strength from Prefrontal Transcranial Direct Current Stimulation Determines Degree of Working Memory Response: A Potential Application of Reverse-Calculation Modeling? Neuromodulation 2022, 25, 578–587. [Google Scholar] [CrossRef] [Scilit]
- Klaus, J.; Schutter, D.J.L.G. Electrode montage-dependent intracranial variability in electric fields induced by cerebellar transcranial direct current stimulation. Sci. Rep. 2021, 11, 22183. [Google Scholar] [CrossRef] [Scilit]
- Pisano, F.; Manfredini, A.; Castellano, A.; Caltagirone, C.; Marangolo, P. Does Executive Function Training Impact on Communication? A Randomized Controlled tDCS Study on Post-Stroke Aphasia. Brain Sci. 2022, 12, 1265. [Google Scholar] [CrossRef] [Scilit]
- Lefaucheur, J.F.; Antal, A.; Ayache, S.S.; Benninger, D.H.; Brunelin, J.; Cogiamanian, F.; Cotelli, M.; De Ridder, D.; Ferrucci, R.; Langguth, B.; et al. Evidence-based guidelines on the therapeutic use of transcranial direct current stimulation (tDCS). Clin. Neurophysiol. 2017, 128, 56–92. [Google Scholar] [CrossRef] [Scilit]
- Monti, A.; Ferrucci, R.; Fumagalli, M.; Mameli, F.; Cogiamanian, F.; Ardolino, G.; Priori, A. Transcranial direct current stimulation (tDCS) and language. J. Neurol. Neurosurg. Psychiatry 2013, 84, 832–842. [Google Scholar] [CrossRef] [Scilit]
- Kunaratnam, N.; Saumer, T.M.; Kuan, G.; Holmes, Z.; Swarbrick, D.; Kiss, A.; Mochizuki, G.; Chen, J.L. Transcranial direct current stimulation leads to faster acquisition of motor skills, but effects are not maintained at retention. PLoS ONE 2022, 17, e0269851. [Google Scholar] [CrossRef] [Scilit]
- Veldema, J.; Gharabaghi, A. Non-invasive brain stimulation for improving gait, balance, and lower limbs motor function in stroke. J. Neuroeng. Rehabil. 2022, 19, 84. [Google Scholar] [CrossRef] [Scilit]
- Darkow, R.; Martin, A.; Würtz, A.; Flöel, A.; Meinzer, M. Transcranial direct current stimulation effects on neural processing in post-stroke aphasia. Hum. Brain Mapp. 2017, 38, 1518–1531. [Google Scholar] [CrossRef] [Scilit]
- Lefebvre, S.; Dricot, L.; Laloux, P.; Desfontaines, P.; Evrard, F.; Peeters, A.; Jamart, J.; Vandermeeren, Y. Increased functional connectivity one week after motor learning and tDCS in stroke patients. Neuroscience 2017, 340, 424–435. [Google Scholar] [CrossRef] [Scilit]
- Welsby, E.; Ridding, M.; Hillier, S.; Hordacre, B. Connectivity as a Predictor of Responsiveness to Transcranial Direct Current Stimulation in People with Stroke: Protocol for a Double-Blind Randomized Controlled Trial. JMIR Res. Protoc. 2018, 7, e10848. [Google Scholar] [CrossRef] [Scilit]
- Carlson, H.L.; Ciechanski, P.; Harris, A.D.; MacMaster, F.P.; Kirton, A. Changes in spectroscopic biomarkers after transcranial direct current stimulation in children with perinatal stroke. Brain Stimul. 2018, 11, 94–103. [Google Scholar] [CrossRef] [Scilit]
- Pruvost-Robieux, E.; Benzakoun, J.; Turc, G.; Marchi, A.; Mancusi, R.L.; Lamy, C.; Domigo, V.; Oppenheim, C.; Calvet, D.; Baron, J.-C.; et al. Cathodal Transcranial Direct Current Stimulation in Acute Ischemic Stroke: Pilot Randomized Controlled Trial. Stroke 2021, 52, 1951–1960. [Google Scholar] [CrossRef] [Scilit]
- Kolskår, K.K.; Richard, G.; Alnæs, D.; Dørum, E.S.; Sanders, A.; Ulrichsen, K.M.; Sánchez, J.M.; Ihle-Hansen, H.; Nordvik, J.E.; Westlye, L.T. Reliability, sensitivity, and predictive value of fMRI during multiple object tracking as a marker of cognitive training gain in combination with tDCS in stroke survivors. Hum. Brain Mapp. 2021, 42, 1167–1181. [Google Scholar] [CrossRef] [Scilit]
- Räty, S.; Ruuth, R.; Silvennoinen, K.; Sabel, B.A.; Tatlisumak, T.; Vanni, S. Resting-state Functional Connectivity After Occipital Stroke. Neurorehabilit. Neural Repair 2022, 36, 151–163. [Google Scholar] [CrossRef] [Scilit]
- Khadka, N.; Borges, H.; Paneri, B.; Kaufman, T.; Nassis, E.; Zannou, A.L.; Shin, Y.; Choi, H.; Kim, S.; Lee, K.; et al. Adaptive current tDCS up to 4 mA. Brain Stimul. 2020, 13, 69–79. [Google Scholar] [CrossRef] [Scilit]
- Chhatbar, P.Y.; Chen, R.; Deardorff, R.; Dellenbach, B.; Kautz, S.A.; George, M.S.; Feng, W. Safety and tolerability of transcranial direct current stimulation to stroke patients—A phase I current escalation study. Brain Stimul. 2017, 10, 553–559. [Google Scholar] [CrossRef] [Scilit]
- Nitsche, M.A.; Paulus, W. Excitability changes induced in the human motor cortex by weak transcranial direct current stimulation. J. Physiol. 2000, 527 Pt 3, 633–639. [Google Scholar] [CrossRef] [Scilit]
- Nitsche, M.A.; Paulus, W.; Frahm, J. Regional modulation of BOLD MRI responses to human sensorimotor activation by transcranial direct current stimulation. Magn. Reson. Med. 2001, 45, 196–201. [Google Scholar]
- Spampinato, M.V.; Chan, C.; Jensen, J.H.; Helpern, J.A.; Bonilha, L.; Kautz, S.A.; Nietert, P.J.; Feng, W. Diffusional Kurtosis Imaging and Motor Outcome in Acute Ischemic Stroke. AJNR Am. J. Neuroradiol. 2017, 38, 1328–1334. [Google Scholar] [CrossRef] [Scilit]
- Lewis, A.F.; Stewart, J.C. Comparison of corticospinal tract integrity measures extracted from standard versus native space in chronic stroke. J. Neurosci. Methods 2021, 359, 109216. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schilling, K.; Gao, Y.; Janve, V.; Stepniewska, I.; Landman, B.A.; Anderson, A.W. Can increased spatial resolution solve the crossing fiber problem for diffusion MRI? NMR Biomed. 2017, 30, e3787. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Behrens, T.E.; Johansen-Berg, H.; Jbabdi, S.; Rushworth, M.F.; Woolrich, M.W. Probabilistic diffusion tractography with multiple fibre orientations: What can we gain? Neuroimage 2007, 34, 144–155. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zheng, X.; Alsop, D.C.; Schlaug, G. Effects of transcranial direct current stimulation (tDCS) on human regional cerebral blood flow. Neuroimage 2011, 58, 26–33. [Google Scholar] [CrossRef] [Scilit]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).