


Abstract
Background: Congenital factor (F) VII deficiency is a rare coagulation factor deficiency with an estimated incidence of 1 per 500,000 individuals. Patients with severe FVII deficiency present a broad range of clinical presentations. Alloimmunization against exogenous FVII, as the main challenge of replacement therapy, is an extremely rare phenomenon that is accompanied by a high rate of life-threatening bleeding, that renders replacement therapy less effective. Due to the importance of the issue, we performed a systematic literature review in order to assess incidence, molecular basis, clinical presentations, and therapeutic challenge and management of inhibitor in congenital FVII deficiency. Strategy of search: This systematic review was performed in accordance with PRISMA guidelines. We performed an English-language literature review in the PubMed, EMBASE, Scopus, and Google Scholar databases, using the following keywords: “factor VII inhibitor”, “factor VII inhibitors”, “FVII inhibitors”, “congenital FVII deficiency”, “recombinant factor VII”, “anti rFVIIa”, “replacement therapy”, and “alloantibody”. Results: Out of 380 patients in the 13 studies, 27 had inhibitor against FVII; 18 were male, 7 were female, while the sex of 2 was not stated. The majority (92%) developed a high-titer inhibitor (Bethesda Unit > 5). All patients had severe FVII deficiency (FVII:C < 10%), and the majority received recombinant FVII prior to inhibitor development (N: 24, 89%). Among ten patients with a detected mutation, three subjects had a common non-sense (30%), and two had a deletion (20%). Conclusions: Inhibitor development is a relatively rare phenomenon seen only in severe FVII deficiency, where it is associated with severe and life-threatening presentations, treatment challenge, and economic burden on the patients and their families.
1. Introduction
Coagulation factor (F) VII is produced by the liver, circulating in the plasma in two forms, mainly as an inactive single chain. It interacts with tissue factor (TF) to initiate the coagulation cascade, more specifically, extrinsic pathway [1,2]. Deficiency of FVII, a rare coagulation factor deficiency (RCFD) is estimated to occur in 1 per 500,000 persons. Incidence of the other RCFDs—fibrinogen, FII (Prothrombin), FV, combined FV and FVIII (F5F8), FX, FXI, FXIII, and vitamin-K-dependent coagulation factor (VKCF)—varies from 1 per 500,000 to 1 per 2,000,000 [2,3]. FVII deficiency, like other autosomal recessive disorders, is more common in societies with a high rate of consanguineous marriages and can be classified, based on FVII coagulation activity (FVII:C), as mild (FVII:C > 20%), moderate (FVII:C 10–20%), or severe (FVII:C < 10%) [4]. Most commonly, FVII deficiency presents with epistaxis, hematoma, intracerebral hemorrhage (ICH), postsurgical bleeding, hemarthrosis, etc. [5].
The mainstay of treatment for congenital FVII deficiency is replacement therapy (RT), available as prothrombin complex concentrates (PCC), fresh frozen plasma (FFP), plasma-derived (pd)-FVII, and recombinant FVII (rFVIIa) [2]. However, RT carries the risk of alloantibody development, which decreases the treatment’s efficacy, requiring more complicated regimens, increases the cost of patient care, and may render the patient disabled [4,6]. Inhibitor, a very serious and life-endangering complication of RT, is an extremely rare phenomenon in FVII deficiency [7]. Due to the paucity of data, as well as the importance of the issue, in the present systematic literature review we aimed to assess incidence, clinical consequences, and management of inhibitor development in patients with congenital FVII deficiency, in order to create a primary scientific structure for further studies in the future.
2. Strategy of Search
This systematic literature review is performed in accordance with PRISMA guidelines. The inclusion criteria and search strategy for study selection were specified in advance. To this end, we analyzed the available literature on congenital FVII deficiency in patients with FVII inhibitor, focusing mainly on different aspects of inhibitor development including incidence, molecular characteristics, clinical presentations, and therapeutic strategy.
A comprehensive English-language search was conducted to identify all published studies (1990 up to the search cut-off date of 1 September 2020) related to our keywords, using the PubMed, EMBASE, Scopus, and Google Scholar electronic databases. Special attention has been paid to the reference list of some of the retrieved items, including eligible articles and recent reviews, to determine existence of additional publications. Our searches used the following keywords: “factor VII inhibitor”, “factor VII inhibitors”, “FVII inhibitors”, “congenital FVII deficiency”, “recombinant factor VII”, “anti rFVIIa”, “replacement therapy”, and “alloantibody”. Keywords were used separately and in combination with each other.
3. Study Selection and Inclusion Criteria
Two-level screening by two of the authors reviewed all non-duplicate citations to evaluate their eligibility for inclusion. Level I, performed by a single reviewer, examined the title and abstract of each article. In Level II, the full text of each citation, evaluated by a single reviewer, then was reviewed by another reviewer. Conflicts or disagreements between the reviewers’ opinions were further analyzed after a thorough discussion on the full text of the source. Thus, a citation was included in our study if both reviewers were in agreement. Selected studies met the following criteria: Only studies on human samples with congenital FVII deficiency were considered; the included studies had a minimum sample size of one patient; the study reported at least one exposure to replacement therapy, especially with rFVIIa. No restrictions were placed on age, sex, ethnicity, or type of replacement therapy.
4. Study Selection
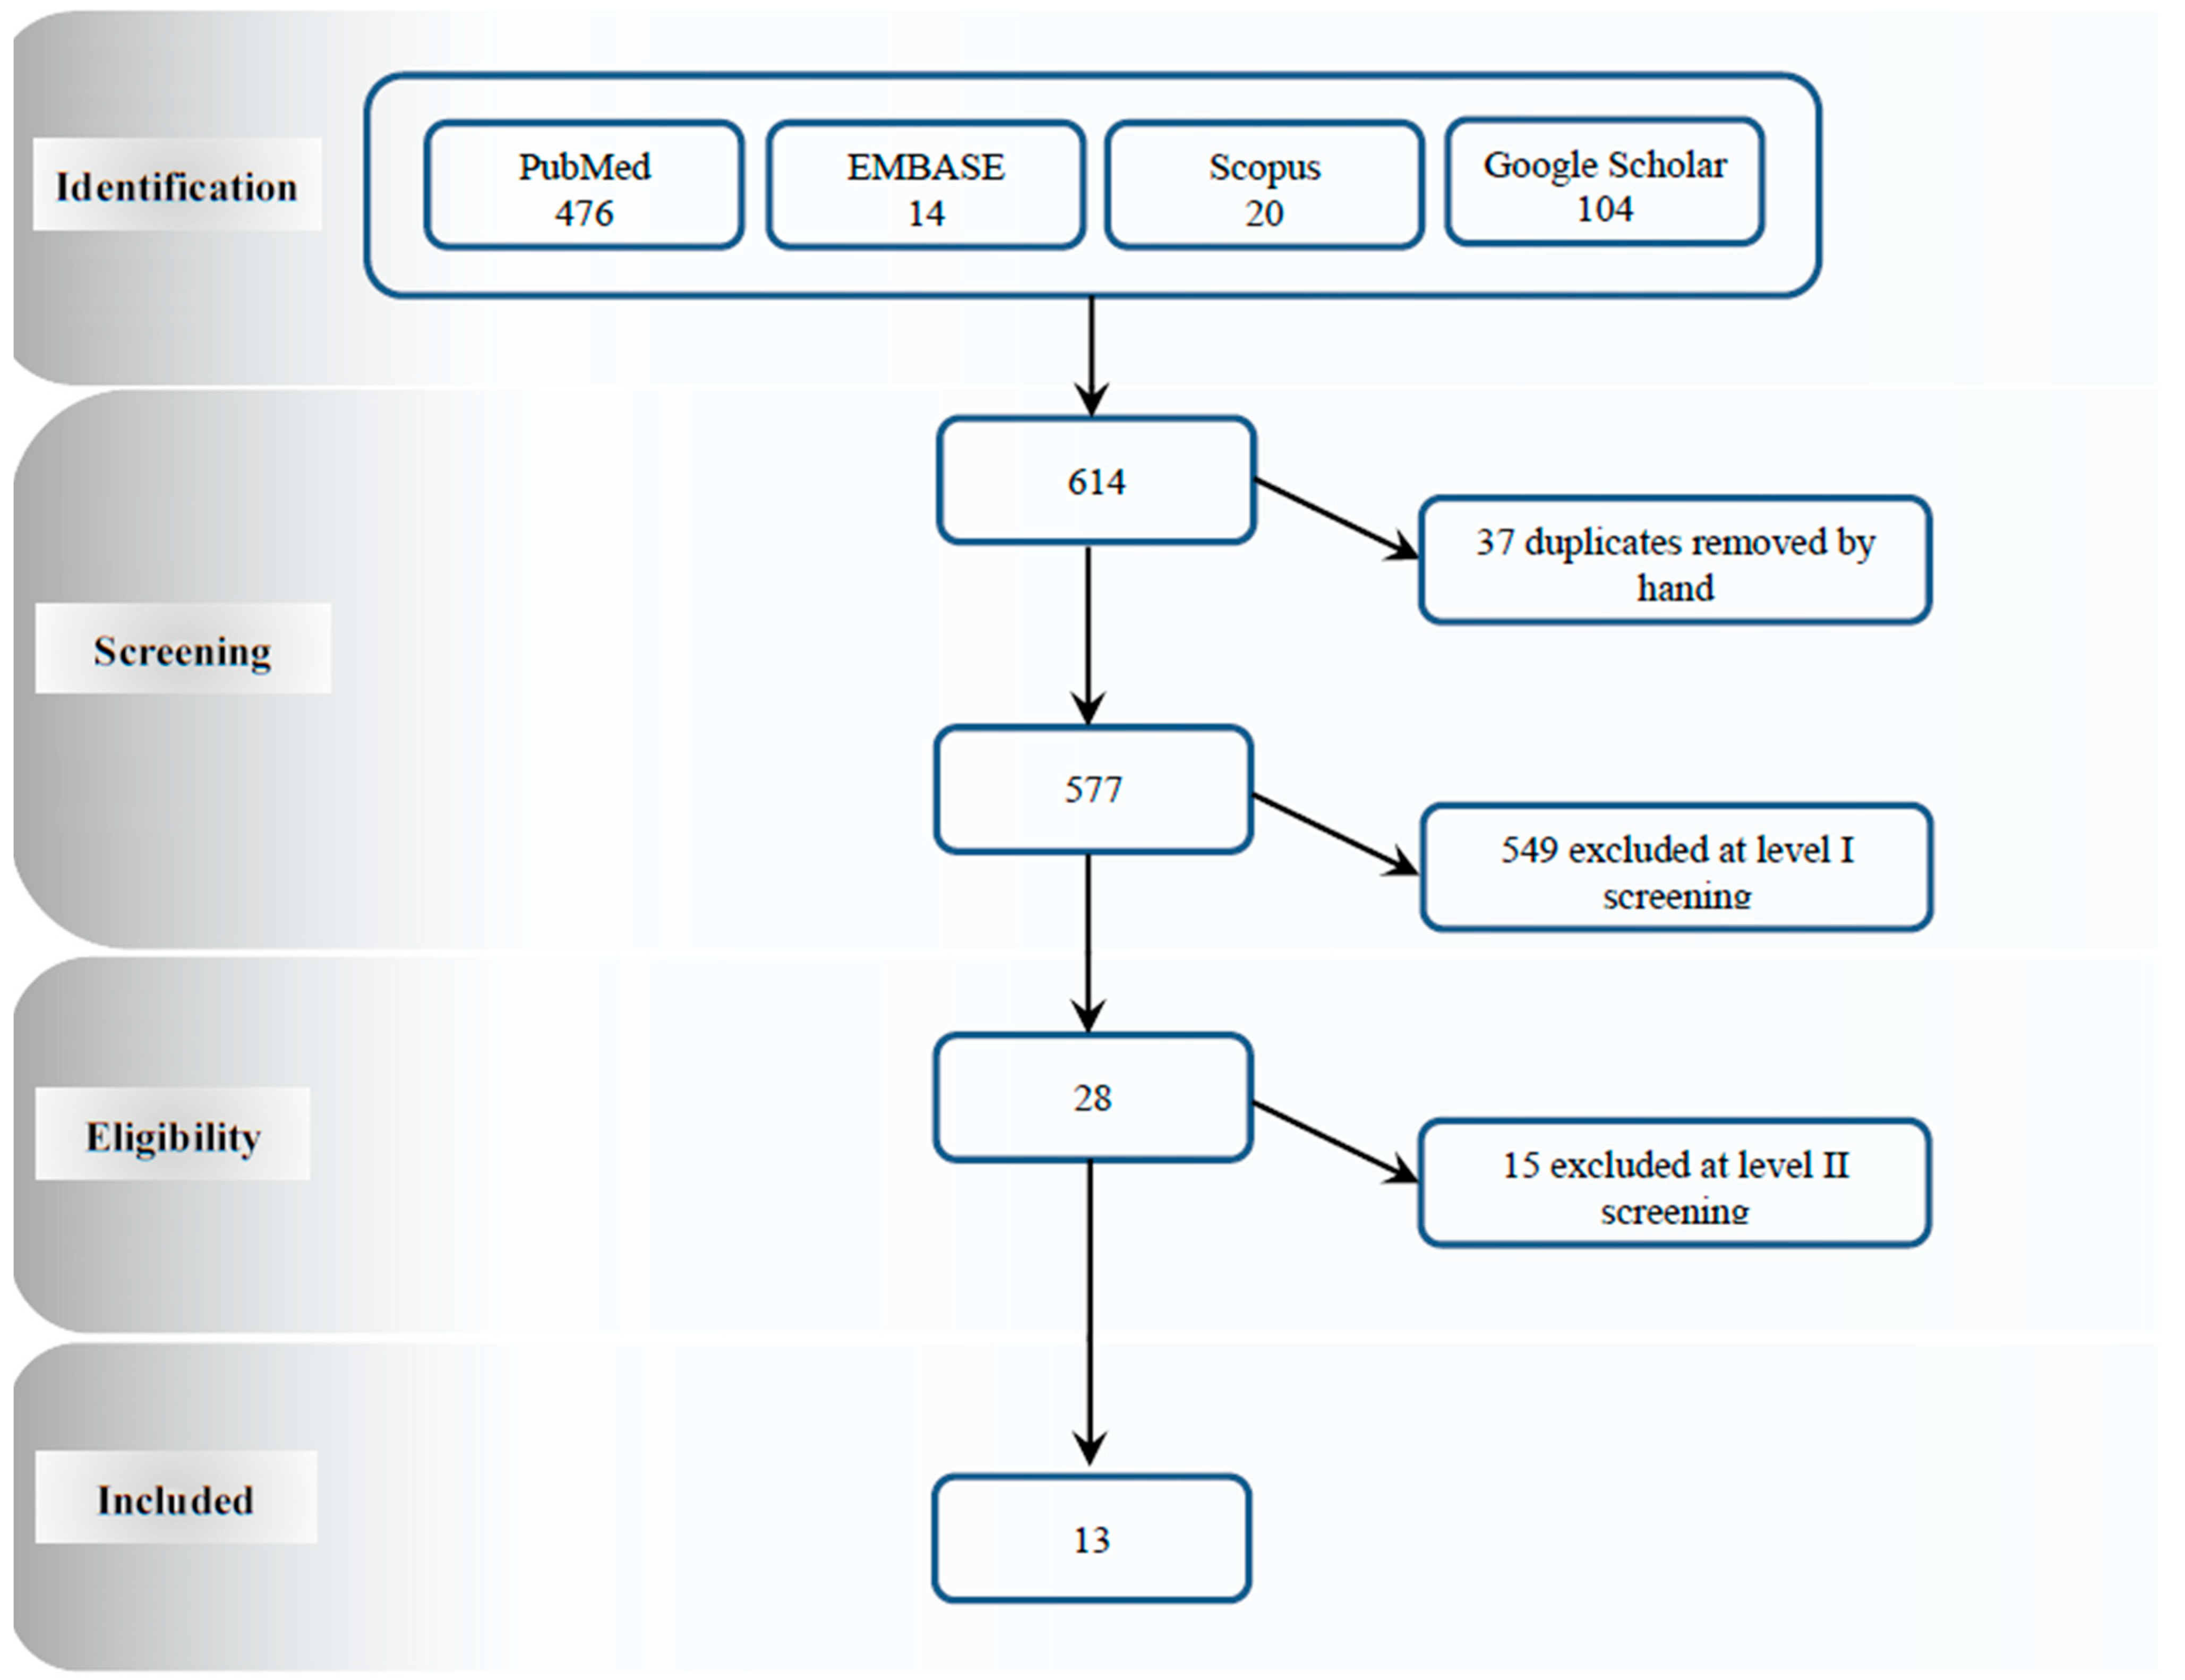
As seen in the flowchart (Figure 1) our search in the mentioned four databases yielded a total of 614 studies. After removing 37 studies, due to duplications, from the list, 577 unique articles were identified, 28 of which were selected following title and abstract screening. Based on our inclusion criteria, 13 studies were found eligible after screening the full texts. Primary reasons for exclusion were: Acquired FVII deficiency, studies on animals, and no exposure to RT.
Figure 1.
Study characteristics and selection.
5. Results
5.1. Study and Patient Characteristics
In the 13 selected studies, 380 patients were identified to have congenital FVII deficiency; among them, 27 were reported to have developed FVII inhibitor. The main characteristics of the patients, including sex, age of study entry, age at deficiency diagnosis, age at inhibitor development, bleeding events, pre/post inhibitor treatment, parental consanguinity, genetics, and antibody titer (Bethesda unit (BU)), are reported in Table 1, Table 2, Table 3, Table 4 and Table 5. All patients with available coagulation FVII levels (N: 26, 100%) had been recognized to have severe congenital FVII deficiency (FVII:C < 10%). Furthermore, 37% (N:10 out of 27) of the patients only received rFVIIa prior to inhibitor development. Similarly, before the inhibitor formation, 7% (N:2 out of 27) of the patients were solely under the treatment with FFP, and 4% (N:1 out of 27) only received pdFVII. 37% (N:10 out of 27) of the patients had the history of receiving both rFVIIa and FFP prior to inhibitor development. For 11% (N:3 out of 27) of the patients had the experience of receiving both rFVIIa and pdFVII as the treatment in their medical history. There was just one patient (N:1 out of 27, 4%) who was under the treatment with all of the three treatments in her medical background. There were 5 (N:5 out of 27, 19%) patients (cases # 1, 18, 21, 25, and 26) who were reported to succumbed to the disease.
Among 27 cases, the age of inhibitor diagnosis was available for 22, among them 73% (N: 16) inhibitor was detected were under the age of five. For four patients, a parental consanguineous marriage had been reported in the literature. In this regard, cases #13 and #18 had a positive history, while cases #14 and #19 had a negative. More than 90% of patients (N: 23 out of 25) had a high-titer inhibitor (BU > 5). The citations identified 18 males and 7 females; one study gave no information about the sex of two patients [8]. Considering the studies in which the age of inhibitor formation has been reported, 5 patients were identified to have developed inhibitor under the age of six months.
Thirty-seven percent (N:10 out of 27) of patients received only rFVIIa prior to inhibitor development. Similarly, before inhibitor formation, 7% (N:2 out of 27) of patients were solely under treatment with FFP, and 4% (N:1 out of 27) received only pdFVII. Thirty-seven percent (N:10 out of 27) of patients had received both rFVIIa and FFP prior to inhibitor development. Eleven percent (N:3 out of 27) had the experience of receiving both rFVIIa and pdFVII as treatment. Just one patient (N:1 out of 27, 4%) was treated with all three substances. Five (N:5 out of 27, 19%) patients (cases # 1, 18, 21, 25, and 26) were reported to have succumbed to the disease.
5.2. Incidence of FVII Inhibitor in Congenital FVII Deficiency
Three studies were performed on the incidence of FVII inhibitors [4,6,9]. The first detailed study is the research of Batorova et al. [6], in the international Seven Treatment Evaluation Registry (STER), with an incidence rate of 2.6% (3 of 115 patients) [6]. The second, performed on 50 Iranian patients by Shams et al. [9], reported an incidence rate of 4% (2 of 50 patients). The most recent study, also conducted on Iranian patients, reported an 8.8% incidence rate (8 of 91 patients) [9]. Compared to previous research, the study of Eshghi et al. [9], has shown a significant increase in the rate of incidence.
5.3. Characterization of the FVII Inhibitor
Regarding the nature and characterization of the FVII inhibitor, we found three research papers in the literature [10,11,12]. Using multiplex assay, Tokgoz et al., [10] assessed the reactivity of antibody, total IgG, and IgG subclasses against rFVIIa. It showed that the alloimmune response was polyclonal and heterogeneous (various IgG subclasses involved); a predominant T helper 2 role in the antibody response to the FVII antigen has been suggested due to the high specificity of the subclass IgG4 [10].
The second study, Branchini et al. [11], confirmed that the immune response was polyclonal; there was a notable predominance of the IgG1 subclass. Another finding of this research was the higher affinity of antibodies toward the active rather than zymogen form of FVII [11].
The third study researched the nature of FVII inhibitor, using an immunoassay based on the x-MAP technology to analyze the isotype of the antibodies against rFVIIa [12]. According to the study’s findings, the high and low specificity of the subclasses IgG1 and IgG3, respectively, suggests a predominant T helper 1 contribution in the alloimmune response. It showed that this response also was polyclonal. It mentioned that, in contrast to their patient, the patient with an IgG4 subclass in the research of Tokgoz et al. [10], has shown a successful response to rFVIIa [10]. All three studies were agreed on the polyclonal nature of the immune system’s response, but only two reported a large predominance of the IgG1.
5.4. Molecular Basis
Among the FVII inhibitor-related studies reported to date, mutations have been reported in 10 out of 27 patients. Notably, no mutation in the coding regions of FVII, or large rearrangement, could be identified in case #13. According to Table 1, Table 2, Table 3 and Table 4, four cases have missense mutations in F7 gene (#3, #4, #14, and #19) (100 GLN ARG shift, Ser103 Gly (S103G), IVS6 + 1G > T, and c.572–12T > A, respectively). Three patients (#5, #10, and #15) have nonsense mutations (p.Ser112-Stop). Patient #9 has a double missense mutation and a single deletion (p.A354V-p.P464Hfs). Two patients (#24 and #26) have c.9711 deletion on exon 7.
Table 1.
Characteristics of 27 FVIID patients with FVII inhibitor (case #1 to #7).
Table 2.
Characteristics of 27 FVIID patients with FVII inhibitor (case #8 to #14).
Table 3.
Characteristics of 27 FVIID patients with FVII inhibitor (case #15 to #21).
Table 4.
Characteristics of 27 FVIID patients with FVII inhibitor (case #22 to #27).
5.5. Clinical Manifestations
Among 27 patients with FVII deficiency and inhibitor, addressed in our systematic review (presented in Table 1, Table 2, Table 3 and Table 4), clinical manifestations had been reported for all cases but one (#2). All 26 patients had FVII:C levels below 10%. About 58% of patients (N: 15) had ICH, 46% experienced epistaxis, 35% had the hematoma phenotype, and 31% showed symptoms of gastrointestinal bleeding. An equal percentage of patients (27%) experienced hemarthrosis or gum bleeding. There was ecchymosis in 15% of the patients, and 8% had hematuria. Among females (7 out of 25—the sexes of two patients (#1 and #2) were not available), two (nearly 28%) reported menorrhagia.
5.6. Management of Inhibitor
According to some case reports and case series, the use of rFVIIa can be either successful or unsuccessful in managing patients regardless of the way it is used (repetitive or single high-dose) [9,13]. Regarding the patients addressed in this study (Table 1, Table 2, Table 3, Table 4 and Table 5), 12 out of 27 (44%) cases were explicitly reported to have been successfully managed with rFVIIa after inhibitor formation (cases 5, 9, 10–12, 14, 15, 16, 20, 22, 23, and 27). Cases 1, 13, 18, 21, and 24–26, however, were not responsive to rFVIIa. Three patients (cases 21, 25, and 26), treated with a high dose of rFVIIa or FEIBA (Factor Eight Inhibitor Bypassing Activity), died due to recurring ICH. Cases 1 and 18, who received only rFVIIa, also died. Case 13 was not responsive to rFVIIa, nor to extensive subsequent immunosuppressive treatment. In case 24, although the patient was unresponsive to rFVIIa (NovoSeven®), the treatment was followed by FEIBA (80–100 IU/kg). An immune tolerance induction (ITI) regimen, pd-FVII concentrate was successfully used to control the inhibitor for case 19. Post-inhibitor treatment with FEIBA elicited excellent clinical response in case 17. Details of the treatment can be found in Table 5.
Table 5.
Treatments and outcomes of patients with FVII inhibitor.
6. Discussion
Regarding inhibitor development in congenital FVII deficiency, few data are available in the literature. The formation of inhibitor to a clotting factor increases the rate of morbidity and mortality, imposes social and spiritual burdens on patients and their families, increases the cost of care, and, in the end, more complications in treatment regimens [18,19]. When it comes to FVII replacement treatment, the development of inhibitory alloantibody against the factor is an important challenge. Patients with FVII deficiency and inhibitor developed a high rate of severe, life-threatening bleeding. About 60% experienced the most dreadful presentation, ICH, whereas the rate for patients without inhibitor is less than 10%. Other major bleeding episodes, such as hematoma, hemarthrosis, and gastrointestinal bleeding, were observed commonly. It seems that inhibitor development aggravates bleeding presentations in FVII deficiency, a finding that was observed in other rare- and common-coagulation factor deficiencies [3]. In addition, as with other factor deficiencies, inhibitor development makes treatment and management of bleeding more challenging, with higher incidence of treatment failure and subsequent death, as reported by Eshghi et al. [9]. Management of bleeding in patients with inhibitor is a significant and sophisticated process, the main goals of treatment being to stop bleeding, and to eradicate inhibitor [4]. In one study on Iranian patients, immunosuppression and eradication of inhibitor had acceptable results. However, the study also observed failure of the treatment, with fatal consequences [9]. The literature review also highlighted that almost all patients with inhibitor had severe FVII deficiency [6,13,14]. In these patients, exogenous infused factor is more likely to be identified as an antigen, leading to immune response and antibody formation. These patients also are more likely to receive RT, due to their higher rate of bleeding [12]. In other coagulation factor deficiencies, such as hemophilia A and B, the rate of inhibitor formation is significantly higher in patients with severe deficiency than mild and moderate deficiencies [20,21]. Similar to hemophilia, the type of replacement therapy, especially with rFVIIa, may play a major role in the complex, multifunctional process of inhibitor formation [11,22]. Although there is a similarity between the gene and protein structures of FVII and FIX, there are some notable differences. For instance, severe gene defects such as large deletion have been reported in patients with hemophilia B with inhibitors; there is no report of such defects in patients with FVII deficiency [23]. Unlike in FVII deficiency, moreover, the immune response in patients with hemophilia B could be complicated by anaphylactoid reaction, which is a severe clinical issue [6,24,25]. Studies conducted on the nature of FVII inhibitor agreed that the type of immune response was polyclonal, with two of the three reporting a predominance of the IgG1 subclass, whereas the third suggested subclass IgG4 [10,11,12].
In the current research we identified 13 studies published from 1990 to 2020 which focus primarily on FVII inhibitor. The aforementioned studies identified 380 patients, among whom 27 developed FVII inhibitor. The incidence rate of FVII inhibitor occurrence, in this group of patients, thus is approximately 7%, which is reasonably close to that reported by Eshghi et al. [9]. This rate of inhibitor formation seems to be higher than that in most RCFDs, but lower than hemophilia A and B [9,21].
Except for two patients (cases #1 and #2) whose sex is not mentioned, 7 patients were female and 18 patients were male; rates of FVII inhibitor occurrence were ~28% and 72%, respectively. The rate of inhibitor development in congenital FVII deficiency seems to be higher in males, but, due to the low number of patients, further studies are required to assess this finding. As can be seen in Table 1, Table 2, Table 3 and Table 4, the genotype of 10 of the 27 patients has been reported in the literature to date. Forty percent of patients had missense mutations (#3, #4, #14, and #20), 30% (#5, #10, and #16) had nonsense mutations, 20% (#21 and #23) had c.9711 deletion on exon 7, and #9 (10%) had a double missense mutation and a single deletion. Although genetic factors might have a role in inhibitor development in FVII deficiency, such a conclusion cannot be reached from available reports due to the small size of the study population. In hemophilia A, genetic risk factors play an important role in inhibitor formation; large deletions, nonsense mutations, and some polymorphisms make the patients more prone to this phenomenon [26,27,28].
Although relatively rare, inhibitor can be formed in congenital FVII deficiency, with life-threatening bleeding, presenting a significant therapeutic challenge which may have fatal consequences. Familiarity with different aspects of inhibitor could help to prevent inhibitor formation and manage this life-threatening condition.
Author Contributions
A.D. conceived the ideas; N.R. and F.Z. searched articles; A.D., N.R., F.Z. collected the data; A.D., N.R., F.Z. and A.B. led the writing. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Acknowledgments
We highly appreciate Daisy Morant’s valuable work in improving the English language of the manuscript.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Franchini, M.; Marano, G.; Mengoli, C.; Piccinini, V.; Pupella, S.; Vaglio, S.; Liumbruno, G.M. Inhibitors in Patients with Congenital Bleeding Disorders other than Hemophilia. Semin. Thromb. Hemost. 2018, 44, 595–603. [Google Scholar] [PubMed]
- See, W.S.; Chang, K.O.; Cheuk, D.L.; Leung, Y.Y.; Chan, G.F.; Chan, S.C.; Ha, S.Y. Inhibitor development after liver transplantation in congenital factor VII deficiency. Haemophilia 2016, 22, e417–e422. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dorgalaleh, A.; Tabibian, S.; Hosseini, M.S.; Shams, M. Pharmacological management of rare coagulation factor deficiencies besides hemophilia. Expert. Rev. Hematol. 2020, 13. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shams, M.; Dorgalaleh, A.; Safarian, N.; Hossein Emami, A.; Zaker, F.; Tabibian, S.; Managhchi, M.R.; Faranoush, M.; Tabatabaei, T.; Satari, S. Inhibitor development in patients with congenital factor VII deficiency, a study on 50 Iranian patients. Blood Coagul. Fibrinolysis 2019, 30, 24–28. [Google Scholar] [CrossRef] [Scilit]
- Mariani, G.; Napolitano, M.; Dolce, A.; Garrido, R.P.; Batorova, A.; Karimi, M.; Platokouki, H.; Auerswald, G.; Bertrand, A.M.; Di Minno, G.; et al. Replacement therapy for bleeding episodes in factor VII deficiency: A prospective evaluation. Thromb. Haemost. 2013, 109, 238–247. [Google Scholar]
- Batorova, A.; Mariani, G.; Kavakli, K.; de Saez, A.R.; Caliskan, U.; Karimi, M.; Pinotti, M.; Napolitano, M.; Dolce, A.; Sørensen, B.; et al. Inhibitors to factor VII in congenital factor VII deficiency. Haemoph. Off. J. World Fed. Hemoph. 2014, 20, e188–e191. [Google Scholar] [CrossRef] [Scilit]
- Napolitano, M.; Dolce, A.; Batorova, A.; Giansily-Blaizot, M.; Ingerslev, J.; Mirbehbahani, N.; Di Minno, M.N.D.; Lopez Fernandez, M.F.; Karimi, M.; Charoenkwan, P.; et al. Replacement therapy in inherited factor VII deficiency: Occurrence of adverse events and relation with surgery. Haemophilia 2015, 21, e513–e517. [Google Scholar] [CrossRef] [Scilit]
- Nicolaisen, E.M.; Hansen, L.L.; Poulsen, F.; Glazer, S.; Hedner, U. Immunological aspects of recombinant factor VIIa (rFVIIa) in clinical use. Thromb. Haemost. 1996, 76, 200–204. [Google Scholar]
- Eshghi, P.; Tara, S.Z.; Baghaipour, M.R.; Bordbar, M.R.; Jenabzade, A.; Habibpanah, B.; Cohan, N.; Tavosi, H.; Bahrami, R.; Karimi, M. Inhibitors against rFVIIa in patients with severe congenital FVII deficiency: A case series. Haemophilia 2019, 25, e345–e349. [Google Scholar] [CrossRef] [Scilit]
- Tokgoz, H.; Caliskan, U.; Lavigne-Lissalde, G.; Giansily-Blaizot, M. Successful prophylactic use of recombinant activated factor VII (rFVIIa) in a patient with congenital FVII deficiency and inhibitors to FVII. Haemophilia 2012, 18, e25–e27. [Google Scholar] [CrossRef] [Scilit]
- Branchini, A.; Baroni, M.; Pfeiffer, C.; Batorova, A.; Giansily-Blaizot, M.; Schved, J.F.; Mariani, G.; Bernardi, F.; Pinotti, M. Coagulation factor VII variants resistant to inhibitory antibodies. Thromb. Haemost. 2014, 112, 972–980. [Google Scholar] [PubMed]
- Borhany, M.; Delbes, C.; Giansily-Blaizot, M.; Zubair, M.; Ahmed, M.S.; Fatima, N.; Shamsi, T. A new report of FVII-inhibitor in a patient suffering from severe congenital FVII deficiency. Haemophilia 2015, 21, e336–e338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ingerslev, J.; Christiansen, K.; SØRensen For the International Registry On Factor Vii Deficiency Steering Committee B. Inhibitor to factor VII in severe factor VII deficiency: Detection and course of the inhibitory response. J. Thromb. Haemost. 2005, 3, 799–800. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pruthi, R.K.; Rodriguez, V.; Allen, C.; Slaby, J.A.; Schmidt, K.A.; Plumhoff, E.A. Molecular analysis in a patient with severe factor VII deficiency and an inhibitor: Report of a novel mutation (S103G). Eur. J. Haematol. 2007, 79, 354–359. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Napolitano, M.; Giansily-Blaizot, M.; Dolce, A.; Schved, J.F.; Auerswald, G.; Ingerslev, J.; Bjerre, J.; Altisent, C.; Charoenkwan, P.; Michaels, L. Prophylaxis in congenital factor VII deficiency: Indications, efficacy and safety. Results from the Seven Treatment Evaluation Registry (STER). Haematologica 2013, 98, 538–544. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tokgoz., H.; Caliskan, Ü.; Blaizot, M.G. Congenital Factor VII Deficiency with Inhibitors to FVII: Report of two Cases. In Haemophilia; WILEY-BLACKWELL: Hoboken, NJ, USA, 2017. [Google Scholar]
- Patel, J.; Tracey Chan, Y.L.; Horgan, C.; Motwani, J. Challenges in the management of congenital Factor VII deficiency with inhibitors. In British Journal of Haematology; WILEY: Hoboken, NJ, USA, 2019. [Google Scholar]
- Bolton-Maggs, P.H. Optimal haemophilia care versus the reality. Br. J. Haematol. 2006, 132, 671–682. [Google Scholar] [CrossRef] [Scilit]
- Franchini, M.; Frattini, F.; Crestani, S.; Bonfanti, C. Alloantibodies in previously untreated hemophilia A patients: The role of environmental factors. Hematology 2013, 18, 183–190. [Google Scholar] [CrossRef] [Scilit]
- Franchini, M.; Lippi, G. Acquired factor VIII inhibitors. Blood 2008, 112, 250–255. [Google Scholar] [CrossRef] [Scilit]
- Bamedi, T.; Dadashizade, G.; Sarabandi, A.; Tabibian, S.; Shams, M.; Dorgalaleh, A. Genetic Risk Factors for Inhibitor Development in Patients with Hemophilia and Rare Bleeding Disorders. J. Cell. Amp Mol. Anesth. 2017, 2, 19–23. [Google Scholar]
- Gouw, S.C.; van der Bom, J.G.; van den Berg, H.M. Treatment-related risk factors of inhibitor development in previously untreated patients with hemophilia A: The CANAL cohort study. Blood 2007, 109, 4648–4654. [Google Scholar] [CrossRef] [Scilit]
- Mariani, G.; Mariani, G.; Herrmann, F.H.; Dolce, A.; Batorova, A.; Etro, D.; Peyvandi, F.; Wulff, K.; Schved, J.F.; Auerswald, G. Clinical phenotypes and factor VII genotype in congenital factor VII deficiency. Thromb. Haemost. 2005, 93, 481–487. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chitlur, M.; Warrier, I.; Rajpurkar, M.; Lusher, J.M. Inhibitors in factor IX deficiency a report of the ISTH-SSC international FIX inhibitor registry (1997–2006). Haemophilia 2009, 15, 1027–1031. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- . Mariani, G.; Konkle, B.; Kessler, C.M. Inhibitors in Hemophilia, A. and B. In Hematology; Hoffman, R., Benz, E.J., Silberstein, L.E., Heslop, H.E., Weitz, J.I., Anastasi, J., Eds.; Basic Principles and Practice; Elsevier: Philadelphia, PA, USA, 2012; Chapter 138; pp. 1961–1970. [Google Scholar]
- Astermark, J.; Oldenburg, J.; Carlson, J.; Pavlova, A.; Kavakli, K.; Berntorp, E.; Lefvert, A.K. Polymorphisms in the TNFA gene and the risk of inhibitor development in patients with hemophilia A. Blood 2006, 108, 3739–3745. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ragni, M.V.; Ojeifo, O.; Feng, J.; Yan, J.; Hill, K.A.; Sommer, S.S.; Trucco, M.N.; Brambilla, D.J. Risk factors for inhibitor formation in haemophilia: A prevalent case-control study. Haemophilia 2009, 15, 1074–1082. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oldenburg, J.; Pavlova, A. Genetic risk factors for inhibitors to factors VIII and IX. Haemophilia 2006, 12, 15–22. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (http://creativecommons.org/licenses/by/4.0/).