Article

Physical and Cognitive Changes After a Gamified Dual-Task Program in Older Adults

Department of Smart Experience Design, Graduate School of Technology Design, Kookmin University, Seoul 02707, Republic of Korea
*
Author to whom correspondence should be addressed.
Appl. Sci. 2026, 16(7), 3133; https://doi.org/10.3390/app16073133
Submission received: 19 February 2026 / Revised: 21 March 2026 / Accepted: 23 March 2026 / Published: 24 March 2026

Abstract

This study employed a gamification-based integrated physical and cognitive program for older adults to examine the applicability of kinematic assessment using a markerless motion capture system (OpenCap version 1.0.1). The program was designed as a step-based dual-task intervention with progressively adjusted difficulty to simultaneously stimulate physical and cognitive functions. Nineteen older adults participated in the study, which evaluated their lower-extremity functional performance (Five Times Sit-to-Stand Test), dynamic balance (Four Square Step Test), curved walking ability (Figure-of-8 Walk Test, F8WT), cognitive function, and program satisfaction. Significant reductions in completion time were observed across all physical performance tests, suggesting within-group improvements in functional performance related to dynamic balance and curved walking ability. Cognitive function also showed significant within-group changes. Kinematic data collected using OpenCap system indicated a significant increase in knee joint angular velocity at the midpoint of the movement, but not in joint range of motion. In addition, high attendance and satisfaction levels were reported. These findings indicate that participation in the gamification-based dual-task program was associated with improvements in several physical performance and cognitive measures in older adults. In addition, the OpenCap system was used as a markerless motion analysis tool to capture movement-related kinematic data.

1. Introduction

South Korea has become a superaged society, one in which the proportion of adults aged 65 years and older exceeds 20% [1]. Falls and fall-related accidents account for approximately 65.1% of injuries among older adults, representing a major public health concern [2]. At the same time, the prevalence of dementia has steadily increased, emphasizing the importance of maintaining both physical and cognitive health in aging populations [3]. Aging is commonly accompanied by declines in both physical and cognitive functions. Reduced lower-limb muscle strength and impaired balance are associated with increased fall risk [4], while cognitive decline negatively affects the performance of activities of daily living and is linked to the progression of dementia. Previous research has suggested that physical activity may contribute to the maintenance of cognitive function [5], and that gait and balance performance are related to cognitive abilities [6]. These findings highlight the interaction between motor and cognitive functions in older adults.
In response to this interaction, exercise programs incorporating simultaneous physical and cognitive tasks have been explored as potential intervention strategies. However, exercise programs for older adults often consist primarily of single-task and repetitive activities that may not fully reflect the combined motor–cognitive demands encountered in everyday situations [7]. In addition, strategies designed to enhance participant engagement during exercise interventions are not always incorporated into program design [8,9].
Gamification has been suggested as an approach to enhance engagement in exercise programs by incorporating game-like elements into physical activity, and some studies have reported improved participation or adherence in certain populations [10]. However, empirical evidence regarding the physical and cognitive effects of gamification-based dual-task exercise programs in older adults remains limited.
Another challenge in intervention research involves the objective measurement of movement characteristics during functional tasks. Traditional physical assessments commonly used in geriatric research provide useful functional indicators but offer limited information about detailed kinematic changes during movement. Markerless motion capture technologies have recently emerged as tools that allow for quantitative measurement of human movement without the need for wearable markers. Among these systems, OpenCap is a machine-learning-based markerless motion capture platform that estimates three-dimensional joint kinematics from videos recorded with multiple smartphone cameras.
Despite the growing availability of such technologies, relatively few studies have integrated markerless motion capture-based kinematic measurements with functional exercise interventions targeting older adults. Furthermore, many exploratory intervention studies in this field have adopted single-group designs to examine preliminary effects of newly developed programs.
Accordingly, the primary objective of this study was to examine changes in physical and cognitive functions in older adults following participation in a gamification-based dual-task intervention program. Additionally, movement data were also collected using OpenCap, a markerless motion capture system, to explore its applicability for capturing kinematic characteristics during functional task performance. This approach may contribute to preliminary insights into the potential use of markerless motion capture technology in offline intervention programs for older adults.

2. Literature Review

2.1. Age-Related Declines in Physical and Cognitive Functions

Advancing age is accompanied by muscle fiber atrophy and decreased neuromuscular activation, leading to sarcopenia and reduced proprioceptive function, as well as declines in balance control and lower limb function, all of which increase the risk of falls in older adults [11,12]. According to injury statistics among older adults in South Korea, falls are the most prevalent cause of major injuries [2]. The empirical verification of interventions aimed at improving lower limb muscular function is thus essential [13]. Substantial research has demonstrated that regular physical activity improves lower limb strength, balance ability, and gait performance, key factors in fall prevention in older adults [14].
Cognitive function also exhibits a gradual decline with aging in multiple domains, such as memory, executive function, and attention, which constitutes a major risk factor for such age-related neurodegenerative conditions as dementia, whose prevalence rates continue to increase [15]. Dementia is closely associated with reduced quality of life and imposes substantial burdens on not only older individuals but their families and society as a whole [16].
Moreover, physical and cognitive functions do not deteriorate independently during aging but are interrelated [17], in line with which, individuals at high risk of dementia who participated in physical activity–based intervention programs exhibited significant improvements in cognitive function and quality of life [18,19]. The interdependence between physical and cognitive domains that these findings indicate suggest that physical stimulation may ameliorate declines in brain activation and spur neurophysiological recovery. Therefore, integrated intervention strategies that simultaneously enhance physical function and provide cognitive stimulation are a necessary part of measures to promote healthy aging.

2.2. Dual-Task Programs and the Stroop Stepping Game

Dual-task paradigms are complex task structures designed to require the simultaneous performance of two tasks. Recent studies have suggested that multimodal interventions combining motor and cognitive training may improve both mobility and executive cognitive function in older adults [20]. Previous studies have also suggested that combined motor and cognitive training can enhance cognitive–motor interaction and improve the ability to perform multiple tasks simultaneously [21].
Dual-task performance demands higher levels of attentional switching, inhibitory control, and executive function than single-task conditions, thereby providing effective stimulation for both physical and cognitive domains. Previous studies have reported a greater effectiveness of dual-task interventions than single-task–based approaches [7]. Moreover, intervention outcomes vary with the presentation order and integration strategy of physical and cognitive tasks [22]. Further, sequential dual-task training in individuals with stroke resulted in limited improvements in cognitive function, but yielded significant enhancements of dynamic balance performance [6].
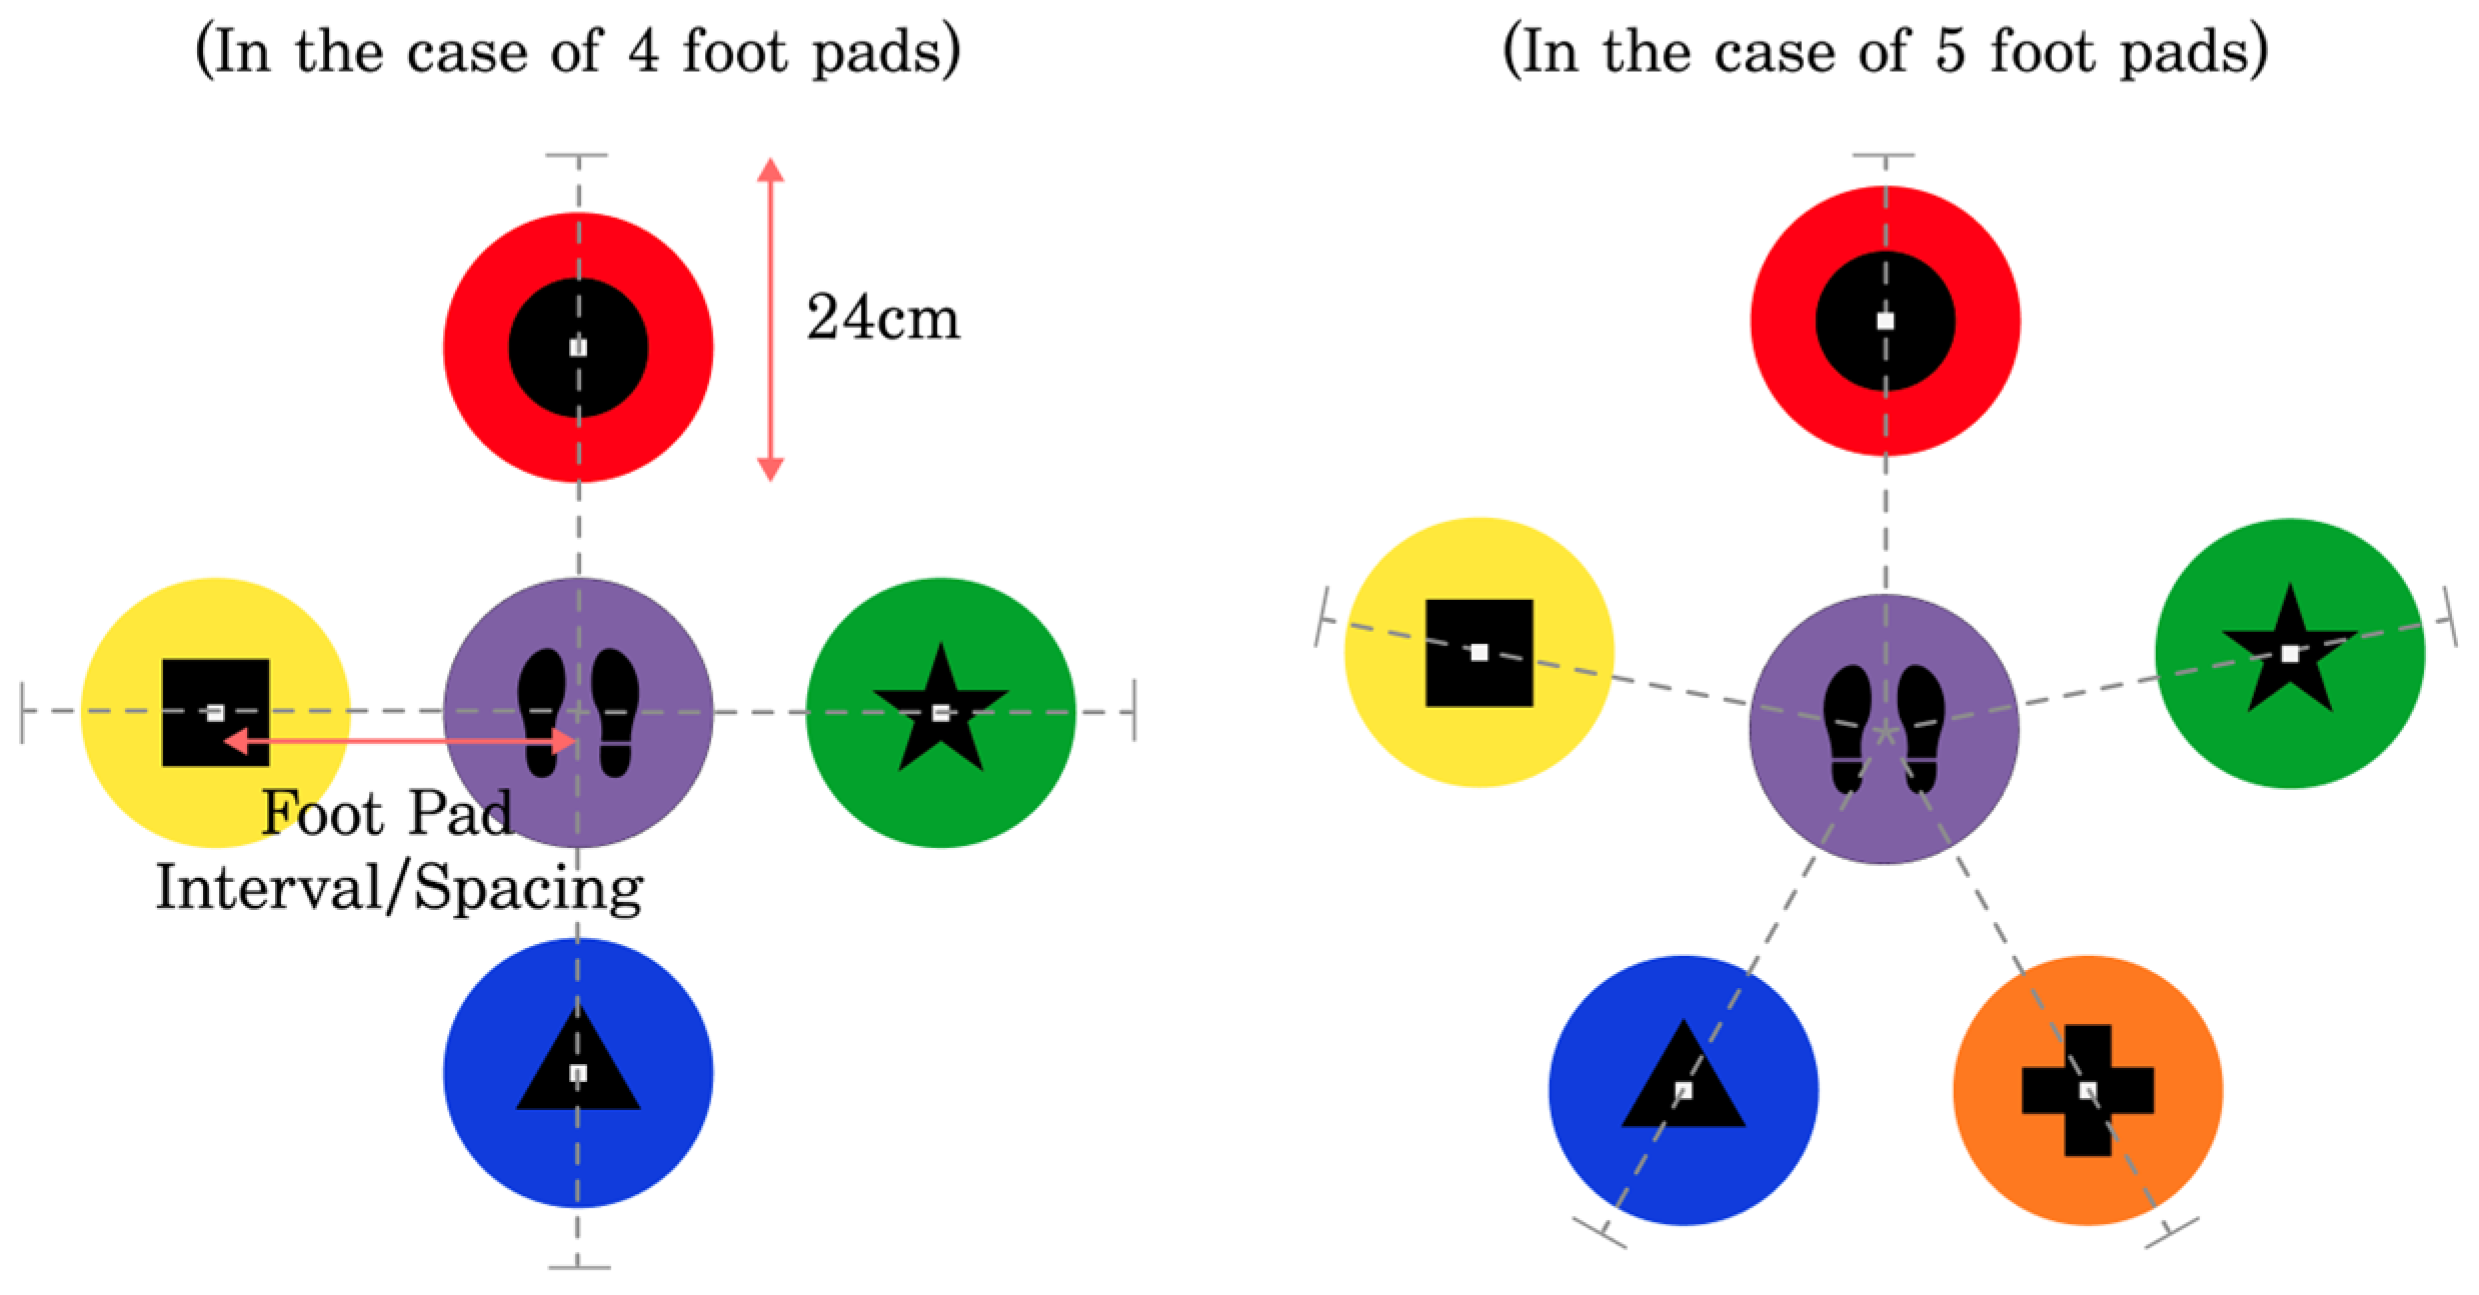
One representative dual-task–based intervention is the Stroop Stepping Game (SSG), which integrates a Stroop task with stepping movements in a game-based program requiring simultaneous cognitive processing and physical responses [22]. Although the traditional well-known Stroop task requires participants to inhibit word meaning while identifying color information, the present approach employed shapes and colors as visual stimuli rather than words in light of the visual processing characteristics of the target population. This design enhances the effectiveness of cognitive training by allowing cognitive load to be manipulated through the use of congruent and incongruent conditions [23].
The present study adapted a color step-based integrated physical and cognitive program to the current research context [22] by expanding and refining the experimental tools, game difficulty design strategies, assessment instruments, and analytical perspectives. The game structure employed in this study is presented in Figure 1.

2.3. Gamification

Gamification is a strategic design approach that applies game elements—such as goals, feedback, rewards, and challenge structures—to nongame contexts to enhance user motivation and engagement [24,25]. This approach promotes both intrinsic and extrinsic motivation [26]. In particular, extrinsic motivation for a high degree of autonomy is associated with positive affective responses and improved performance outcomes [26]. Previous studies of older adults have identified competition, rewards, and feedback as effective gamification elements that play a critical role in sustaining participation in physical activity programs [27]. Nevertheless, a lack of motivational design elements sufficient to effectively support long-term user engagement has been reported in the healthcare domain [28].
Several studies have reported that gamification-based exercise programs have benefits for physical function in older adults, including improvements in gait speed and stride length, as well as increasing individuals’ willingness to participate in physical activity [29]. However, as many of these studies conducted only short-term interventions or lacked appropriate control groups, they were generally unable to adequately verify long-term behavioral changes or cognitive improvement effects [30].
Furthermore, gamification design for older adults requires a systematic and structured approach that extends beyond simple entertainment features. In South Korea, the need for theoretical frameworks and empirical validations of effectiveness has been increasingly emphasized in recent years with expansions in the practical applications of gamification [31]. In light of the rapid progression of population aging and the growing prevalence of cognitive decline, the motivational role of gamification in programs designed to enhance physical and cognitive functions in older adults has gained increasing importance.
The present study applies gamification strategies in an integrated physical and cognitive program for older adults and evaluates their empirical effects. In particular, we measured the effectiveness of the proposed program through gait-related physical performance measures and changes in cognitive function, providing foundational evidence for the design of effective gamification-based interventions to promote healthy aging.

2.4. A Machine-Learning-Based Markerless Motion Capture System: OpenCap

Conventional marker-based three-dimensional motion capture systems have been widely used as standard tools for acquiring precise movement data in clinical and biomechanical research. However, these systems have several limitations, including complex marker placement procedures, expensive recording equipment, and strict environmental constraints that limit their applicability in real-world settings [32]. To address these limitations, markerless motion capture technologies have recently emerged that employ camera-based video data and machine-learning algorithms to estimate three-dimensional human movement without the need for physical markers, allowing for more natural movement assessment and greater flexibility in experimental environments [33]. Among these approaches, OpenCap, developed by Stanford University, has been introduced as a smartphone-based markerless motion capture system for estimating human movement kinematics. Previous validation studies comparing OpenCap with conventional marker-based motion capture systems have reported high levels of agreement in key gait parameters such as walking speed and stride length, supporting the reliability of markerless motion capture for gait analysis [34,35]. However, most previous studies have focused on fundamental locomotor tasks such as walking or running, and evidence regarding the applicability of OpenCap to more complex movement assessments, including dynamic balance tasks, remains limited.

3. Materials and Methods

3.1. Study Design

3.1.1. Research Model

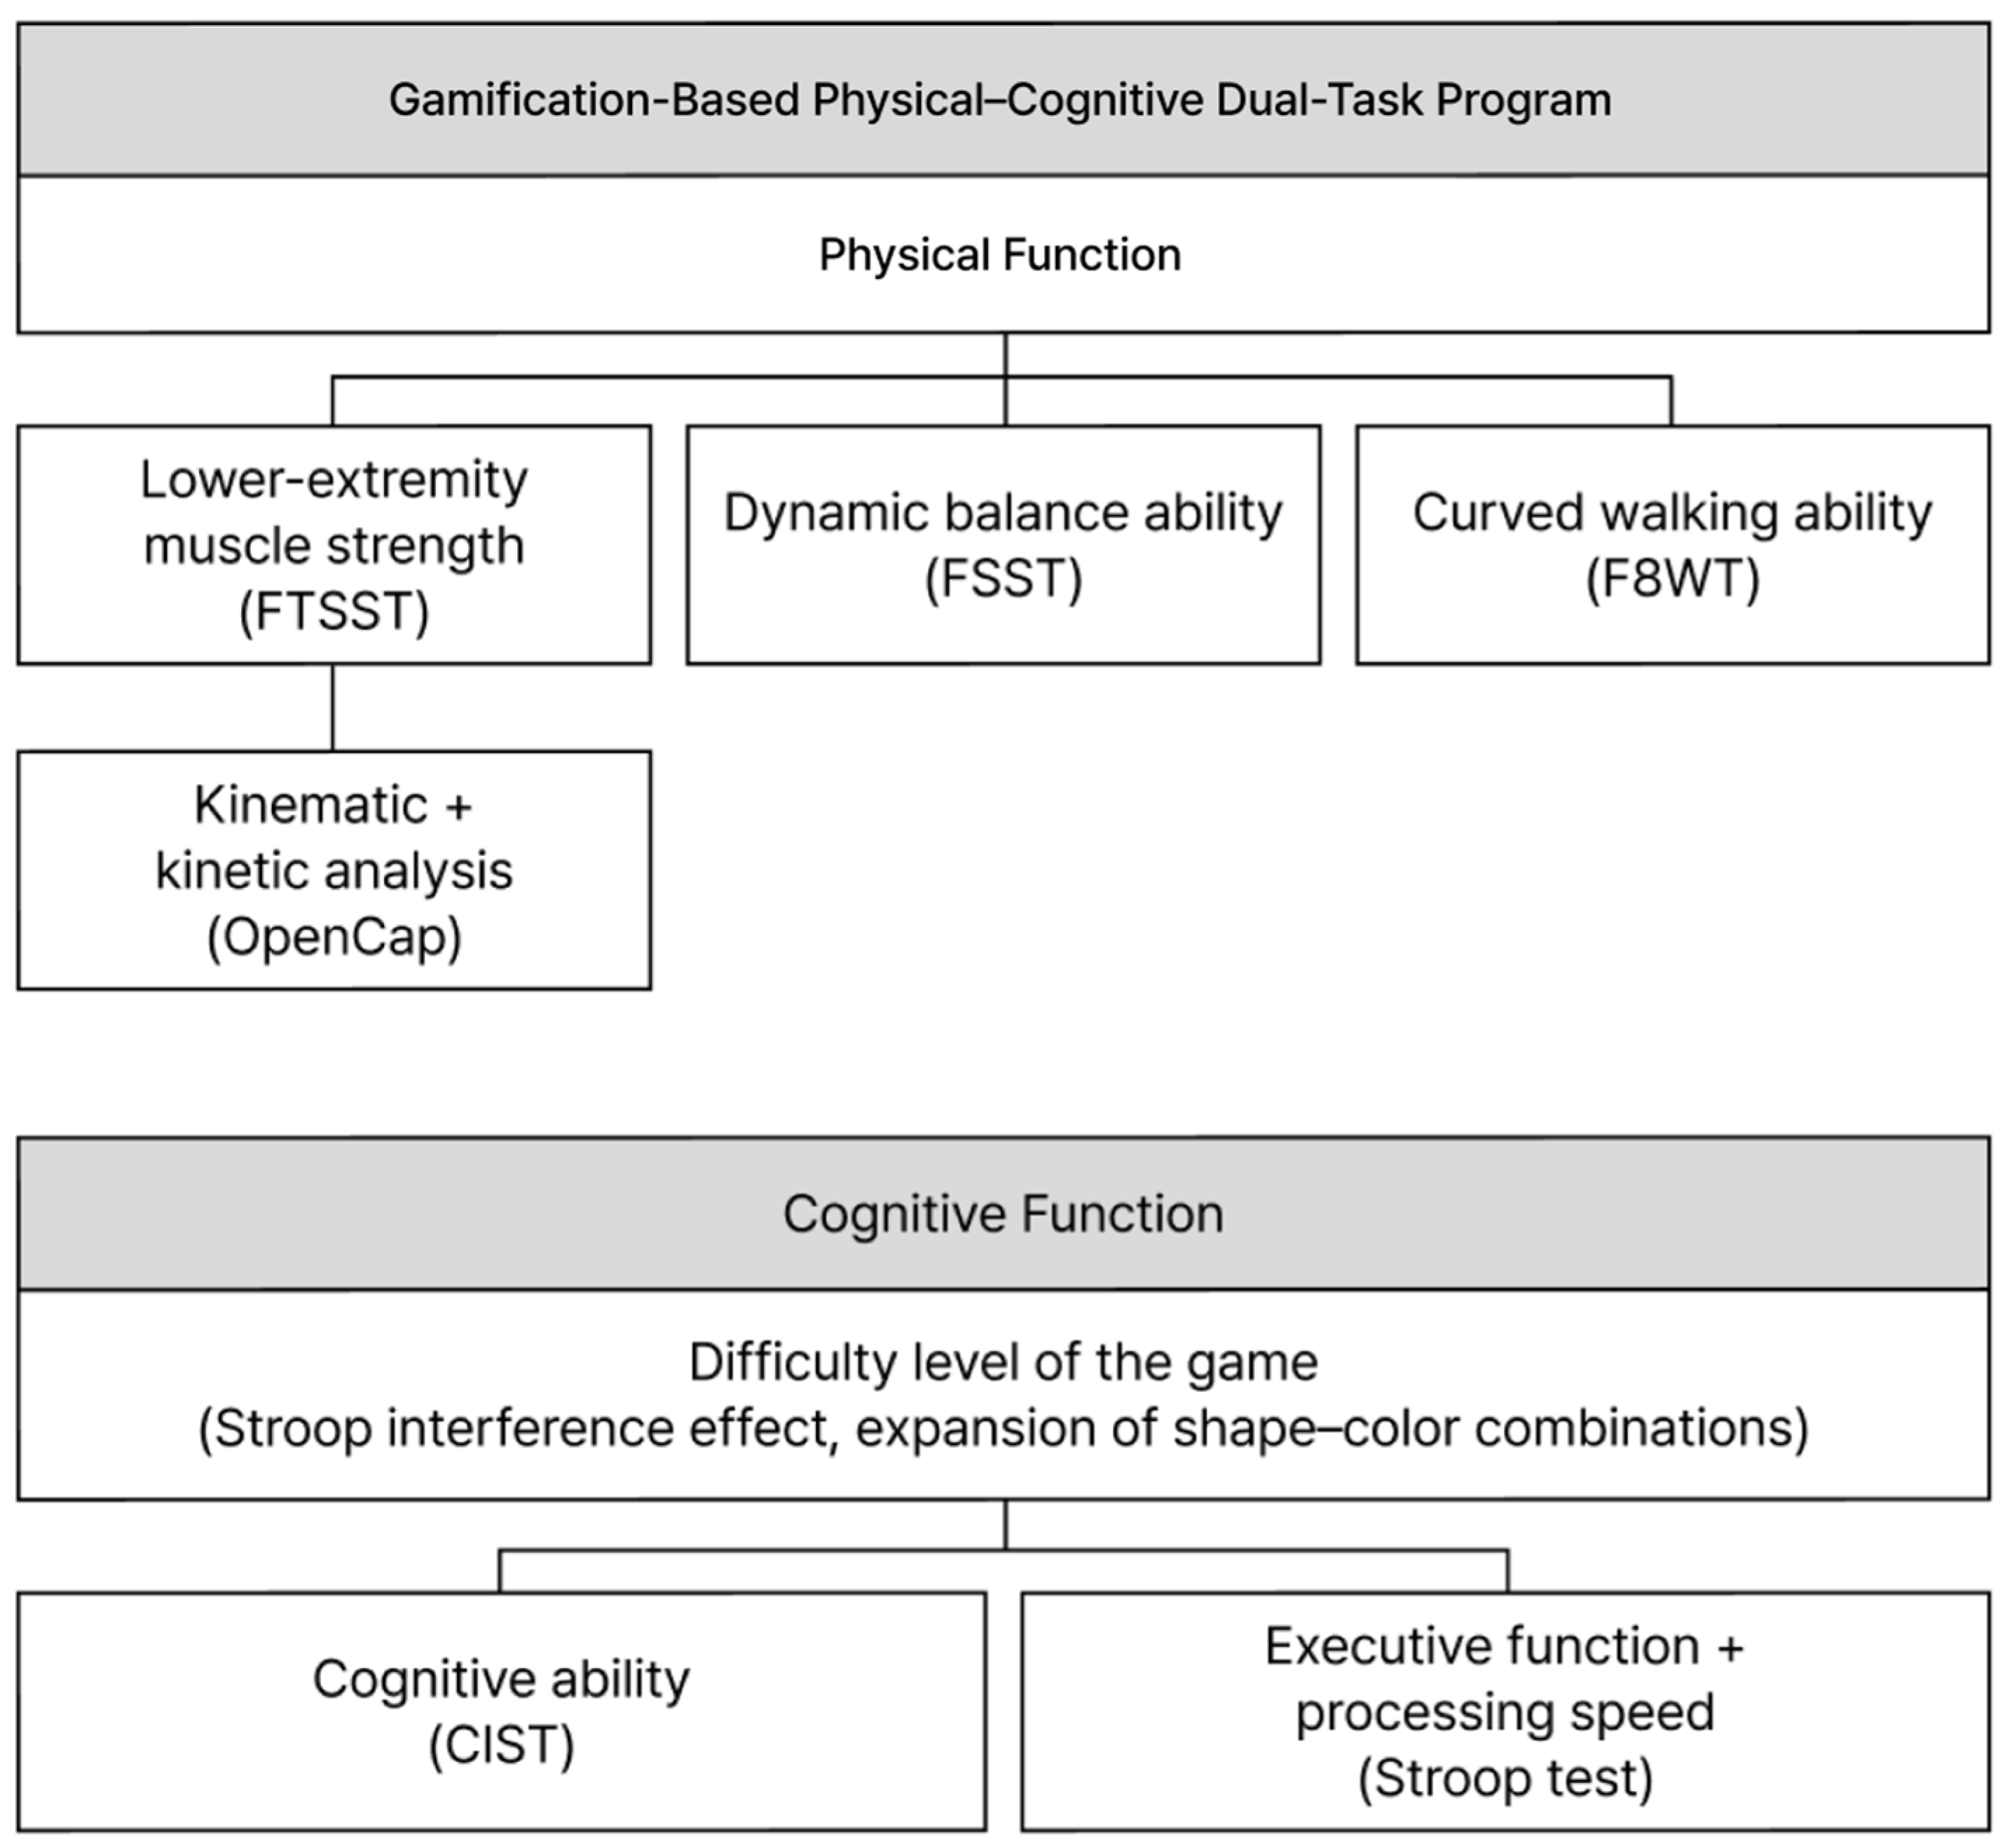
Figure 2 illustrates the conceptual framework of the present study. The gamification-based physical–cognitive dual-task program was designed to influence both physical and cognitive functions in older adults. Physical function outcomes included lower-extremity muscle strength, dynamic balance ability, and curved walking performance, which were assessed using the Five Times Sit-to-Stand Test (FTSST), the Four Square Step Test (FSST), and the Figure-of-8 Walk Test (F8WT), respectively.
In addition, OpenCap-based markerless motion capture was used to obtain exploratory kinematic indicators during the FTSST task. Cognitive function was assessed using the Cognitive Impairment Screening Test (CIST) and the Stroop test to evaluate executive function and processing speed.

3.1.2. Research Questions

This study aimed to develop and implement a gamification-based integrated physical and cognitive dual-task program for older adults and examine changes in physical and cognitive functions before and after the intervention. The effectiveness of the program was evaluated using a multidimensional assessment framework.
In addition, OpenCap-based markerless motion capture was used as a complementary analytical tool to obtain exploratory kinematic indicators alongside conventional physical function assessments. Furthermore, this study explores the applicability and scalability of gamification-based intervention programs for older adults and provides foundational evidence for the design of digital-technology-supported exercise assessment and intervention strategies in aging populations.
This study posited the following Research Questions:
RQ 1. Lower-extremity muscle strength in older adults is expected to improve following participation in the integrated physical–cognitive dual-task program.
RQ 2. Dynamic balance ability in older adults will show significant improvement over the course of the integrated physical–cognitive dual-task program.
RQ 3. Curved walking ability in older adults will show significant improvement over the course of the integrated physical–cognitive dual-task program.
RQ 4. Cognitive function in older adults will show significant improvement over the course of the integrated physical-cognitive dual-task program.
RQ 5. OpenCap-based markerless motion capture will provide exploratory kinematic indicators that may complement conventional physical function assessments in older adults.
RQ 6. Participants are expected to maintain active participation throughout the intervention period.

3.2. Participants

This study included 24 older adults aged 65 years or older who attended the J Silver Welfare Center in Seongbuk-gu, Seoul, in 2025. This sample size reflects the maximum number of participants that could be realistically recruited given the practical constraints associated with enrolling older adults in a longitudinal intervention study. The intervention program was conducted over 11 weeks, and participants were recruited on a voluntary basis.
This study was approved by the Institutional Review Board of Kookmin University (IRB No. KMU-202509-HR-504). Written informed consent was obtained from all participants prior to participation.
The inclusion criteria for study participants were as follows:
  • The ability to communicate independently without assistance from others;
  • Normal vision, excluding individuals who required corrective lenses;
  • No color vision deficiency;
  • No diagnosis of dementia;
  • No hearing impairment, with the use of hearing aids permitted.
As five participants withdrew during the study period for personal reasons, a total of 19 participants completed the program and were included in the final analysis. Recruiting and retaining older adults for longitudinal intervention studies is inherently challenging because of age-related physical limitations, variability in health status, scheduling constraints, and the burden associated with repeated participation over time. In the present study, participants were required to attend repeated training sessions and outcome assessments over an extended period, which imposed substantial practical demands. Considering these feasibility constraints, the final sample of 19 participants was regarded as acceptable for a preliminary repeated-measures intervention study involving adults aged 65 years and older. The characteristics of the final study sample are presented in Table 1.

3.3. Intervention Protocol

3.3.1. Program Structure and Overview

The program was conducted twice per week for a total of 20 sessions. Each session was administered face-to-face by one researcher and one social worker in the auditorium of the welfare center and lasted approximately 50–55 min. Although the total study schedule spanned 11 weeks, the active intervention period was 8 weeks. The remaining time included participant orientation, pre- and post-intervention assessments, and a one-week interruption due to the temporary closure of the participating institution.
Following this interruption, the latter phase of the intervention resumed with an increased pad distance according to the planned progression of task difficulty.
Each session was structured as an integrated physical–cognitive task, incorporating repetitive stepping activities and response-based components. In the individual tasks, participants were guided to perform an average of approximately 455 steps, whereas in the group tasks, the target was approximately 400 steps. In the group tasks, the number of steps performed per participant was adjusted based on the number of attendees in each session.
The cognitive task was structured based on participants’ responses. When a participant correctly performed the required stepping task, the next stimulus was presented after an interval of approximately 3 s. In cases of incorrect responses, the same task was repeated. This structure allowed the task progression to adapt to individual performance speed and encouraged active engagement in both cognitive and motor components.
An overview of the program is presented in Table 2 and Table 3.
The program was organized into three sequential phases—preparation, individual competition, and group competition—with scheduled rest periods. During the preparation phase, participants’ physical condition on the day of the session was checked and light warm-up exercises were performed to prevent safety incidents, thereby ensuring adequate physical readiness and environmental preparation for program participation.
In the individual competition phase, the start of the game was signaled by rhythmic music, followed by approximately 25 min of the individual game “Match It! Color Step”. Six stepping pads (diameter: 24 cm) made of SEBS material were used. Participants remained at their individual positions and completed tasks by recognizing the shape and color of stimuli presented on a screen and selecting the corresponding stepping pad. The researcher observed the participants’ performance and provided immediate feedback throughout the phase. Upon completion of the individual competition, performance results were shared to reinforce participants’ sense of achievement. This phase was followed by an approximately 5-min rest period, during which, the next game was announced.
The group competition phase lasted approximately 15 min. In each session, participants were randomly divided into two teams. Each team performed tasks sequentially as displayed on a front-facing screen in a relay format, passing a Styrofoam ring to the next team member upon task completion. The rules were explained before the group competition and mutual encouragement among team members was promoted to enhance cooperation and motivation. The team that completed all the tasks first was designated the winning team, and points were awarded on the individual scoreboards accordingly. After the group competition, information on the next session was announced, followed by closing remarks.
An overview of the overall program structure and the operational layouts of the individual and group competition phases are presented in Supplementary Table S1 and Table 4, and Figure 3.
Game difficulty was progressively adjusted based on both physical and cognitive components. Physical difficulty was determined by increasing the distance between the stepping pads according to the participants’ average step length. The initial interpad distance was set at 45 cm and was increased by 5 cm at four-session intervals, gradually increasing the physical load across sessions.
Cognitive difficulty was manipulated by applying congruent and incongruent conditions of the Stroop task. From the ninth session onward, an orange (+) stepping pad was introduced, expanding the number of pads and simultaneously increasing cognitive and physical task demands. To minimize task adaptation and learning effects, the arrangement of the stepping pads was rotated clockwise across sessions. This difficulty-adjustment strategy was applied consistently to both the individual and group competition phases. The difficulty structure across game sessions is summarized in Supplementary Table S2.

3.3.2. Gamification Strategies Within the Program

The program incorporated several gamification elements to enhance motivation and sustained participation among older adults, including competition, achievement, rewards, and social interaction. A point-based system and personal leaderboard were used to provide feedback on participation and encourage continued engagement without imposing excessive competitive pressure. Achievement was supported through attendance-based scoring and visual feedback on task progression throughout the program. Participants also received individualized feedback on assessment results and a small completion reward to reinforce their sense of accomplishment. In addition, team-based activities and peer encouragement were incorporated to promote social interaction and foster group cohesion during the intervention.
An overview of the gamification strategies applied in the program is presented in Table 5.

3.3.3. Intervention Development

We conducted interviews with four domain experts to identify key elements of a dual-task program for older adults that need modification and refinement. Interviews on program composition were conducted with one specialist in rehabilitation medicine and one expert in sports rehabilitation and biomechanics, while interviews on the application of OpenCap involved one biomedical engineering researcher and one researcher from a laboratory specializing in aging and exercise science.
All the experts consistently emphasized the importance of task designs that consider dynamic balance in addition to lower-extremity function, the inclusion of cognitive assessments that capture cognitive processing speed, the application of progressive difficulty adjustments, and measures to ensure participant safety throughout the program. Based on these expert recommendations, the present study extended the scope of physical function assessment in Chung (2025) [36] to include dynamic balance and curved walking performance and further enhanced the cognitive evaluation framework by incorporating a Stroop Test.
Based on expert consultation derived from interviews with a biomechanics specialist, the Five Times Sit-to-Stand Test (FTSST) was selected for OpenCap-based kinematic analysis in this study. Compared to more complex tasks such as the FSST and F8WT, FTSST was considered to involve relatively fewer occlusion-related situations during task performance. Given the known limitations of markerless motion capture under occlusion conditions, this characteristic made FTSST a more suitable task for analysis. Accordingly, FTSST was applied for exploratory kinematic analysis using OpenCap in the present study.

3.4. Measurements

3.4.1. Physical Performance Measures

  • The Five Times Sit-to-Stand Test
The FTSST is a widely used functional assessment of lower limb strength and dynamic balance. Participants sit on a chair without armrests and maintain an upright posture without leaning against the backrest, with their arms crossed over the shoulders. Upon the examiner’s signal to begin, participants perform five consecutive sit-to-stand movements as quickly as possible. The time is recorded from the initial movement until the final seated position is achieved. One practice trial is provided before the formal assessment. Shorter completion times indicate superior lower limb strength and balance performance. The Five Times Sit-to-Stand Test has demonstrated excellent test–retest reliability in older adults (ICC = 0.937) [37].
  • Four Square Step Test
The Four Square Step Test (FSST) is a functional assessment incorporating elements such as directional changes, obstacle avoidance, and agility that comprehensively evaluates balance and functional mobility. In this test, four canes are arranged on the floor in a cross formation to create four quadrants. Participants begin in quadrant 1 and step sequentially to quadrants 2, 3, 4, and back to quadrant 1 in a clockwise direction, after which the same sequence is repeated in a counterclockwise direction. If a participant touched a cane or performed the sequence incorrectly, the trial was repeated. One practice trial was provided, followed by three recorded trials. Shorter completion times indicate superior functional mobility and dynamic balance control. The Four Square Step Test has shown excellent reliability in older adults (ICC = 0.994) [38].
  • Figure-of-8 Walk Test (F8WT)
The Figure-of-8 Walk Test (F8WT) is a curved walking assessment tool used to evaluate fall risk in older adults and verify rehabilitation outcomes in individuals with neurological and musculoskeletal conditions. Two cones are placed approximately 1.5 m apart, and participants start from the midpoint between the cones, around the front cone in a counterclockwise direction, and then around the rear cone in a clockwise direction, forming a figure-of-eight walking pattern. The time required to return to the starting position was recorded. This test differs from linear gait assessments in that it reflects direction-changing walking demands encountered in daily life. One practice trial was provided, followed by three recorded trials. Shorter completion times indicate superior curved walking ability. The Figure-of-8 Walk Test has demonstrated excellent reliability in older adults (ICC = 0.987) [38].
All physical performance assessments used in this study have demonstrated excellent test–retest reliability in previous studies.

3.4.2. Cognitive Measures

  • Cognitive Impairment Screening Test (CIST)
The Cognitive Impairment Screening Test (CIST) is a standardized cognitive assessment tool developed by the Ministry of Health and Welfare of Korea and is officially used in the national dementia management program. The test is administered one-on-one between the examiner and the participant using a paper-based questionnaire. It assesses six cognitive domains: orientation, attention, visuospatial ability, executive function, memory, and language, with a total score of 30 points, where higher scores indicate better cognitive function. Because normative ranges differ by age and years of education, the interpretation of identical total scores may depend on the participant’s demographic background. The Cognitive Impairment Screening Test (CIST) is a cognitive screening tool developed by the Korean Ministry of Health and Welfare and the National Institute of Dementia and is currently used in dementia safety centers in Korea.
In this study, the CIST was only administered pre- and post-intervention. This decision was based on the standardized use of the CIST as a periodic cognitive screening tool, typically conducted at relatively long intervals (e.g., annual assessments) to minimize potential practice effects and maintain assessment validity.
Given the duration of the intervention in this study, repeated administration of the CIST within the study period was considered inappropriate as it could affect the validity of the assessment. Therefore, the CIST was used exclusively to evaluate overall cognitive status before and after the intervention.
  • Stroop Test
The Stroop Test is a cognitive assessment tool used to evaluate cognitive flexibility, processing speed, and executive function in older adults. The test consists of three conditions administered using separate test sheets, each containing 100 word or color stimuli.
The Stroop Test was administered at three time points (pre-intervention, mid-intervention, and post-intervention) using the same test sheets across all assessments. Although alternate forms were not used, sufficient time intervals between assessments were maintained as part of the intervention schedule to reduce potential practice effects associated with repeated testing. All testing procedures, instructions, and administration conditions were kept consistent across the three measurement points.
The repeated administration of the Stroop Test was intended to capture short-term changes in executive function during the intervention period. As a widely used neuropsychological measure, the Stroop Test is commonly used to assess short-term changes in attention and cognitive control and is suitable for repeated assessments within relatively short intervals. Therefore, multiple time-point measurements were conducted to monitor the progression of cognitive changes throughout the intervention. Previous research has reported high reliability of the Stroop test, with intraclass correlation coefficients (ICC) ranging from 0.833–0.901 [39].
  • The word-reading condition requires participants to read color names printed in black ink.
  • The color-naming condition requires participants to name the color of stimuli presented without any word content.
  • The incongruent word–color condition presents color words printed in incongruent ink colors, and participants are instructed to ignore the word meaning and respond only to the ink color.

3.4.3. Motion Capture Analysis

  • OpenCap
OpenCap is an open-source, machine-learning–based markerless motion capture system developed by a research team at Stanford University that estimates three-dimensional joint kinematics and kinetics from videos recorded using two or more iOS device cameras. In the present study, OpenCap was employed to collect and analyze movement data during task performance in older adults.
To capture participants’ movements from multiple perspectives, task performance videos were recorded using two iOS devices. Camera calibration was performed using a printed checkerboard provided on the OpenCap website to ensure accurate spatial alignment between cameras. The recorded video data were subsequently uploaded to the cloud-based processing server of OpenCap, where automated motion analysis was conducted.
OpenCap processes uploaded videos using deep learning-based pose estimation algorithms to extract two-dimensional anatomical keypoints from each frame. These keypoints are reconstructed into three-dimensional joint coordinates through triangulation across multiple camera views [40]. The extracted kinematic data were then temporally synchronized and processed using Python (version 3.9.6)-based numerical analysis. The movement cycle was subsequently normalized, and angular velocity and velocity-related parameters were calculated based on temporal changes in knee joint angles.
Based on expert consultation derived from interviews with a biomechanics specialist, OpenCap-based kinematic analysis was applied exclusively to the Five Times Sit-to-Stand Test (FTSST). This decision was made because FTSST was considered to involve relatively fewer occlusion-related situations during task performance compared to more complex tasks.
From the FTSST video recordings, knee joint range of motion and velocity-related metrics (vel_RoM and vel_time) were extracted. In addition, angular velocity and velocity parameters at 25%, 50%, and 75% of the movement cycle were analyzed to compare changes in knee joint kinematic characteristics before and after participation in the intervention program. The final variables were statistically analyzed using IBM SPSS (version 29.0.2).
However, depending on individual movement patterns, partial occlusion of body segments may still occur, which could affect tracking accuracy. Therefore, the kinematic results should be interpreted with caution, and OpenCap was used as a complementary and exploratory measurement tool.

3.4.4. Program Satisfaction Evaluation

A participant satisfaction survey was administered after the completion of the program, consisting of a questionnaire with total of 18 items: 16 closed-ended and 2 open-ended questions. Participants completed the survey using a self-administered format, and the closed-ended items were scored on a 5-point Likert scale. Only the responses to the closed-ended questions were used in a quantitative analysis of overall levels of program satisfaction.

3.4.5. Assessment Schedule and Measurement Timeline

This study aimed to examine changes in physical performance and cognitive function across the intervention period through assessments conducted before, during, and after program participation. Because the overall study schedule included both the active intervention period and a one-week interruption related to institutional closure, the observed temporal patterns should be interpreted as reflecting the broader study timeline rather than a strictly uninterrupted 8-week training sequence.
Accordingly, the FTSST, FSST, F8WT, and Stroop Test were administered three times: pre-intervention, mid-intervention, and post-intervention.
OpenCap-based kinematic data were collected across the three assessment sessions; however, due to practical constraints related to motion capture recording conditions and data quality control, only the pre- and post-intervention datasets were included in the final kinematic analysis.
All assessments were conducted face-to-face at the same welfare center. The overall assessment timeline is presented in Table 6.

3.5. Statistical Analysis

Statistical analyses were performed using IBM SPSS Statistics (version 29.0.2). Descriptive statistics, including means and standard deviations, were calculated for all variables. A repeated-measures ANOVA was conducted to examine changes across the three measurement points (pre-, mid-, and post-intervention). The assumption of sphericity was assessed using Mauchly’s test, and when violated, the Greenhouse–Geisser correction was applied. In such cases, the adjusted degrees of freedom were used and are reported accordingly in the results. Post hoc pairwise comparisons were conducted using estimated marginal means (EMMs) with Bonferroni correction to adjust for multiple comparisons. Normality of the data was assessed using the Shapiro–Wilk test. Statistical procedures were selected based on the distributional characteristics of the data. Statistical significance was set at p < 0.05.
It should be noted that the sample size was determined based on feasibility considerations rather than an a priori power calculation. Given the one-group repeated-measures design, within-subject changes over time could be detected more efficiently than in independent-group comparisons because between-subject variability was reduced. Effect sizes were reported as partial eta-squared (η2p). The observed time effects for the primary physical outcomes were statistically significant and associated with large effect sizes (FTSST: η2p = 0.395; FSST: η2p = 0.477; F8WT: η2p = 0.378).
To provide additional context, a post hoc power analysis was conducted using G*Power (version 3.1.9.7) based on the observed effect sizes. Based on the observed η2p values, the corresponding Cohen’s f values exceeded the conventional threshold for a large effect, and the analysis suggested that approximately 9–10 participants would have been sufficient to detect the time effect under standard assumptions. Therefore, the final sample of 19 participants was statistically sufficient (power ≥ 0.80) to detect the observed within-subject changes over time.

4. Results

All statistical analyses were conducted using IBM SPSS Statistics (version 29.0.2). For the main variables collected at the pre-, mid-, and post-intervention time points, descriptive statistics, including means and standard deviations, were first calculated to display overall trends. To test for statistically significant changes over time, repeated-measures ANOVA was conducted, and estimated marginal means (EMMs) were used for post hoc comparisons. The assumption of sphericity was assessed using Mauchly’s test, and when the assumption was violated, the Greenhouse–Geisser correction was applied. Changes in performance associated with increasing stepping-pad distance were visually examined using EMM plots.

4.1. Physical Function Outcomes

4.1.1. Inbody, FTSST, FSST, and F8WT

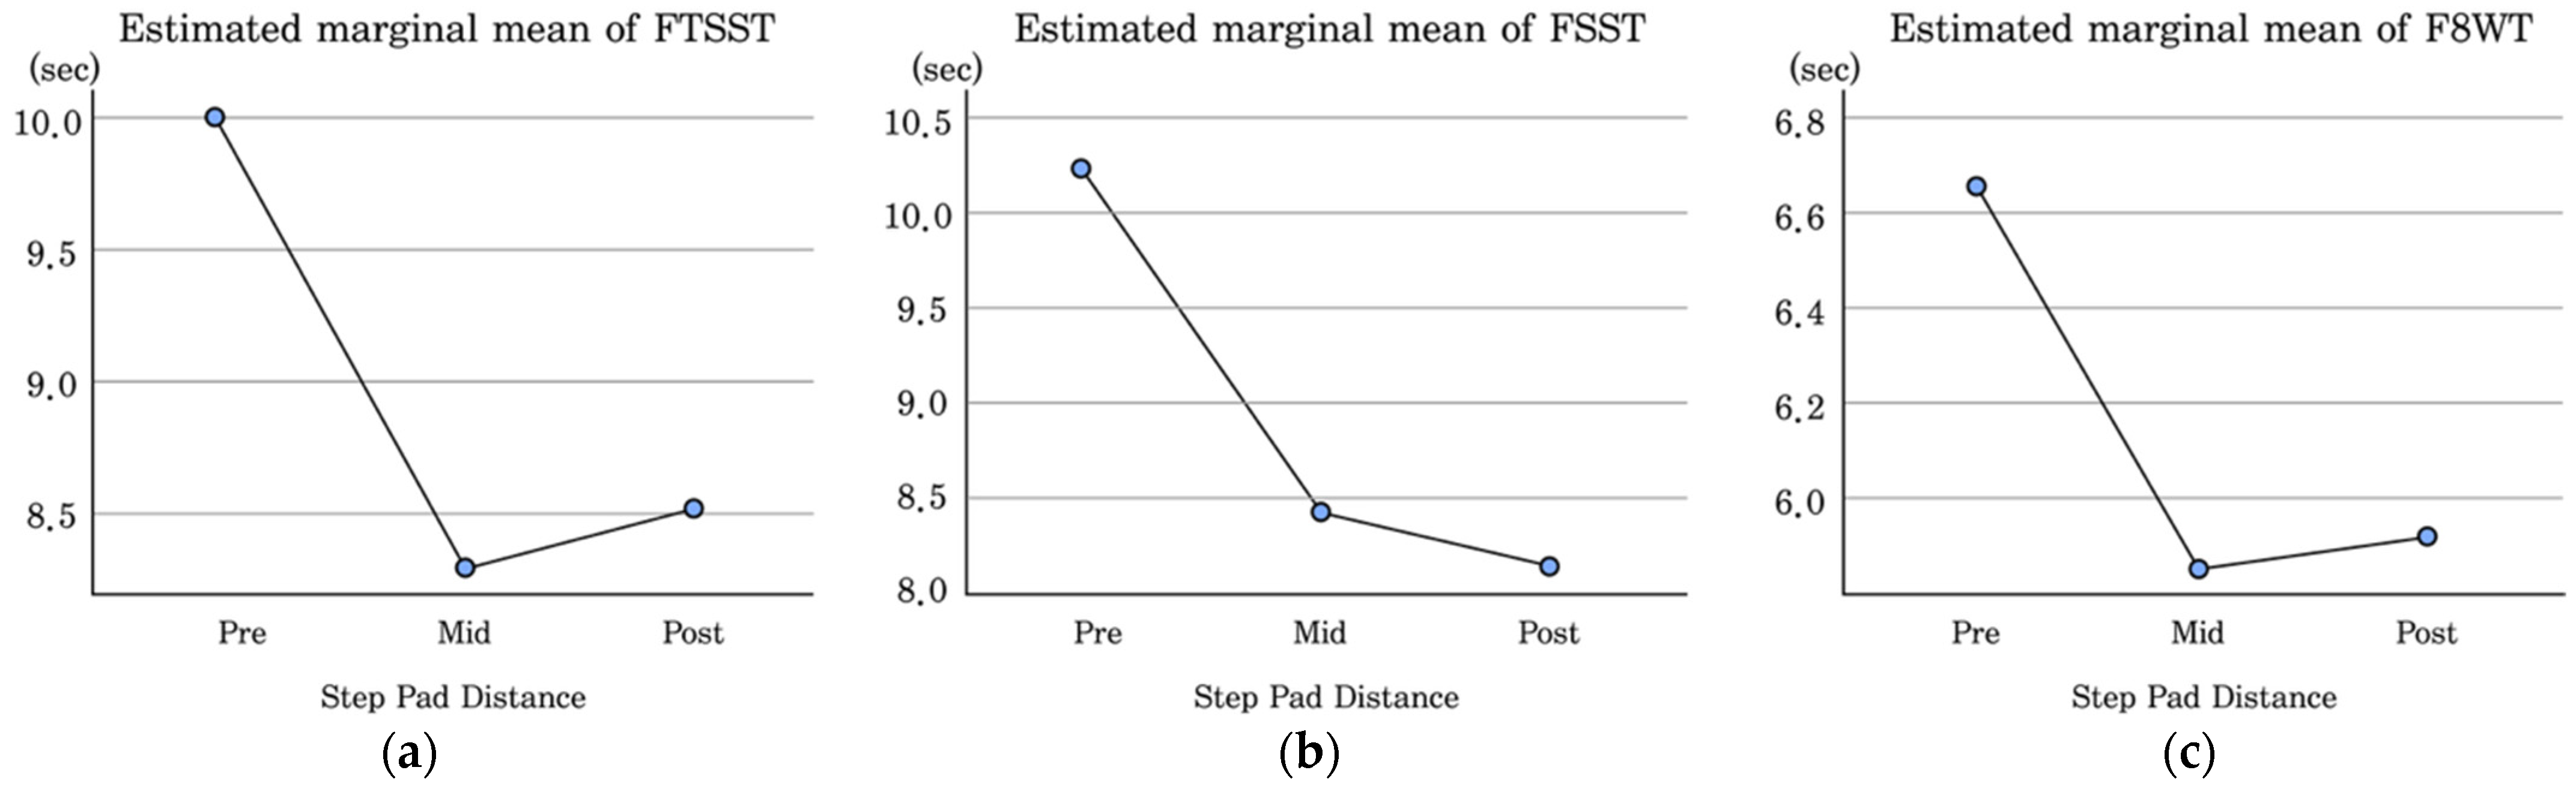
For the analysis of physical performance, stepping-pad distance was treated as the independent variable, and changes in lower limb strength (FTSST), dynamic balance (FSST), and curved walking ability (F8WT) were examined. Descriptive statistics across the three time points indicated a general pattern in all measures of decreased completion times with increased stepping-pad distance.
Repeated-measures analysis revealed statistically significant differences across time points for all physical function measures, including FTSST (p < 0.001, η2p = 0.395), FSST (p < 0.001, η2p = 0.477), and F8WT (p < 0.001, η2p = 0.378). These findings indicate that participation in the program was associated with improvements in lower limb strength, dynamic balance, and curved walking ability over time. However, because the latter phase of the program involved both a progression in stepping-pad distance and an interruption-related gap in training continuity, the observed temporal changes should not be interpreted as reflecting the isolated effect of pad-distance progression alone. The changes in participants’ InBody measurements and the means and standard deviations of the FTSST, FSST, and F8WT scores are presented in Table 7, Table 8 and Table 9.
An examination of the effects of increased stepping-pad distance on physical performance revealed that all three physical indicators demonstrated the most pronounced improvements between the pre- and mid-intervention stages, suggesting that the increased task difficulty resulting from a 5-cm expansion in the stepping-pad distance effectively stimulated such functional components as lower limb strength, dynamic balance, and curved walking ability.
A more detailed analysis showed that both the FTSST and F8WT exhibited a slight increase in completion time post-intervention; however, performance levels remained improved over the baseline. In contrast, the FSST showed a continuous decrease in completion time through to post-intervention, indicating a relatively stable pattern of functional improvement.
These results suggest that physical adaptations were most prominent during the early phase of the program and tended to stabilize during the later stages. Furthermore, the stepwise adjustment of task difficulty using incremental increases in stepping-pad distance appears to have functioned as an effective intervention mechanism. The EMMs of FTSST, FSST, and F8WT across time are presented in Figure 4.

4.1.2. OpenCap

In this study, kinematic data for joint angles and task completion time collected during the FTSST were analyzed. First a signal stabilization procedure was applied, after which, the sit-to-stand movement was segmented into five repeated cycles. To minimize interindividual variability at the beginning and end of task performance, the first and fifth repetitions were excluded from the analysis; only the second, third, and fourth repetitions were used for pre–post comparisons.
To account for differences in movement speed across participants, time normalization was applied to each repetition and angular velocity values of the joint angles at 25%, 50%, and 75% of movement progression were extracted and analyzed.
To examine the distribution of each variable, the Shapiro–Wilk test of normality was conducted. The results indicated that, at baseline, the total range of motion (RoM; p = 0.004), joint angles (p = 0.047), and angular velocities (p = 0.026) at the 75% phase of the movement did not satisfy the assumption of normality.
Accordingly, paired-samples t-tests were applied to variables that met the normality assumption and the Wilcoxon signed-rank test was applied to the others. The results of the Shapiro–Wilk normality tests for joint angles and angular velocities across movement phases are presented in Table 10.
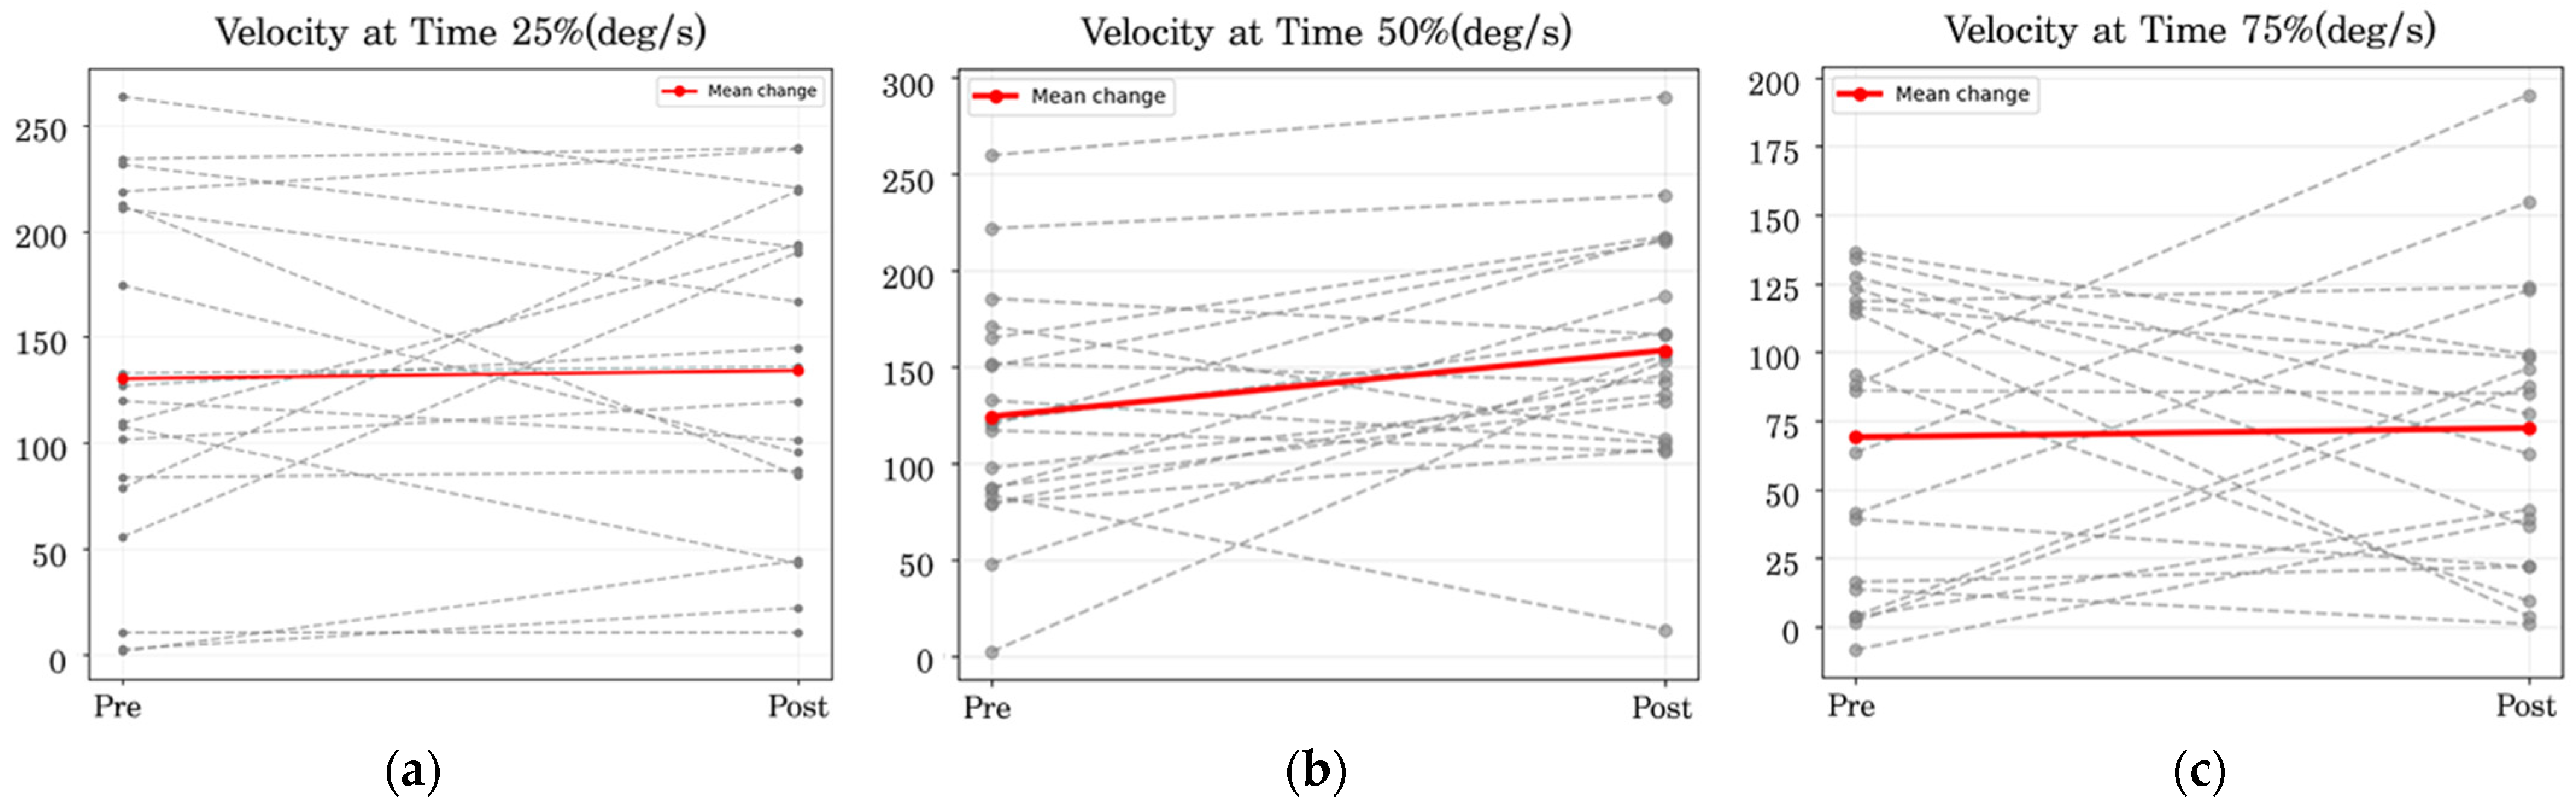
T-tests found no statistically significant pre–post differences for joint RoM at the 25% (p = 0.710, Cohen’s d = 0.087) and 50% (p = 0.982, Cohen’s d = 0.01) phases, nor for angular velocity at the 25% phase (p = 0.686, Cohen’s d = 0.094), while at the 50% phase, angular velocity showed a statistically significant increase over baseline in the post-intervention assessment (p = 0.018, Cohen’s d = 0.6). This result indicates that a significant change was only observed in angular velocity at the 50% phase of the movement cycle.
Overall, the findings suggest that changes in movement velocity were limited to a specific phase of the movement cycle and were not consistently observed across all phases.
The paired-samples t-test results for joint angles and angular velocities at the 25% and 50% phases are presented in Table 11.
Wilcoxon signed-rank tests found no statistically significant pre–post difference in knee joint RoM (p = 0.629, Cohen’s d = 0.102), suggesting that the intervention had a limited effect on the magnitude of joint angle excursion. In addition, angular velocity at the 75% phase based on RoM showed an increasing trend in the post-intervention assessment over baseline; however, this difference did not reach statistical significance (p = 0.07, Cohen’s d = 0.495). Similarly, no significant pre–post difference was observed for the angular velocity at the 75% phase (p = 0.872, Cohen’s d = 0.05).
The results of the Wilcoxon signed-rank tests for overall joint angles and for joint angles and angular velocities at the 75% movement phase are presented in Table 12.
These findings indicate considerable interindividual variability in movement speed regulation during FTSST performance.
Although some kinematic indicators showed directional changes, these changes did not reach statistical significance at the group level.
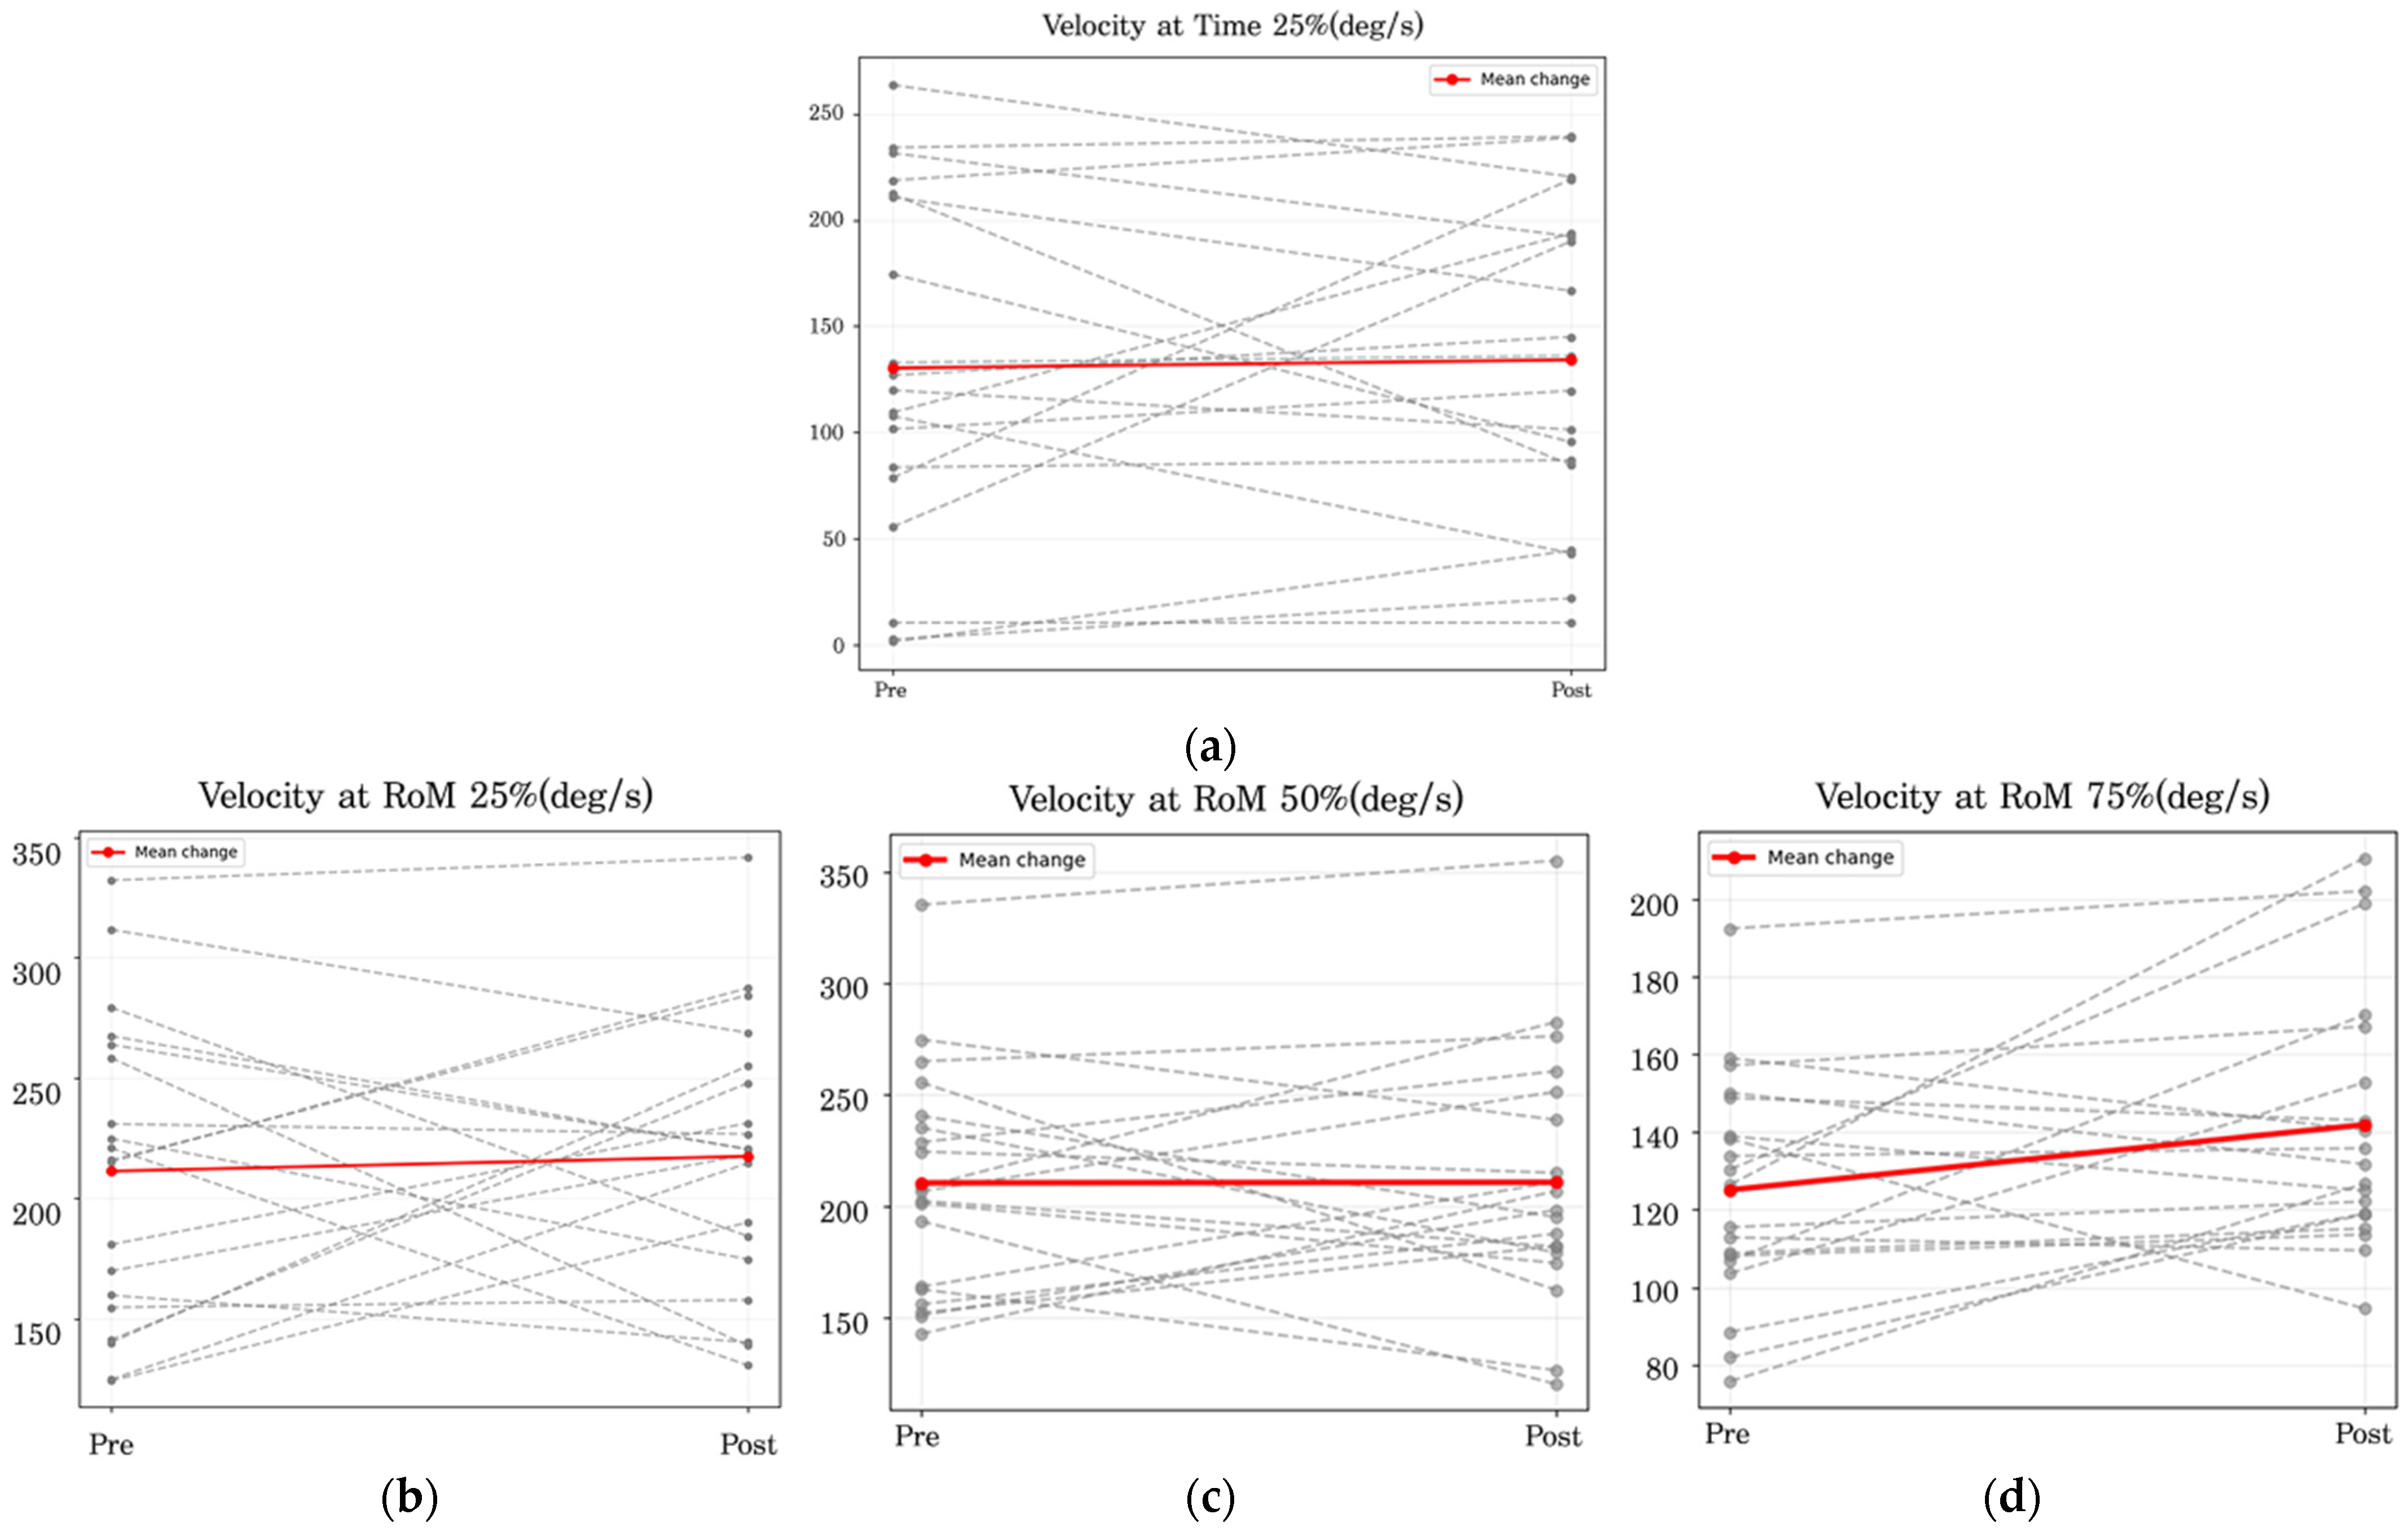
For a more intuitive illustration of pre–post changes, paired line plots were generated for each kinematic variable in which the solid red line represents the trajectory of the group mean and the gray dashed lines indicate individual participants’ change patterns. The direction of individual changes was inconsistent for all variables, with overall patterns reflecting either slight increases or maintenance of baseline levels. These visual patterns were consistent with the results of the statistical analyses.
Notably, among the analyzed kinematic parameters, only angular velocity at the 50% phase showed a statistically significant change between the pre- and post-intervention assessments.
Graphical representations of changes in knee joint RoM and angular velocity are presented in Figure 5 and Figure 6.

4.2. Cognitive Function Outcomes

4.2.1. CIST

The analysis of cognitive function revealed a statistically significant increase in the total cognitive score following the intervention (p = 0.012, Cohen’s d = 0.64). Among the subdomains, significant improvements were observed in executive function (p < 0.001, Cohen’s d = 1.24) and memory (p = 0.028, Cohen’s d = 0.55), which may be interpreted as the result of repeated exposure to the Stroop-based game activities and diverse cognitively demanding tasks embedded in the program, which provided direct stimulation of specific cognitive abilities.
In contrast, no significant differences were observed in other subdomains, including orientation, attention, and language function, suggesting that the program exerted selective effects on cognitively demanding domains like executive function and memory, rather than producing uniform improvements across all aspects of cognitive function.
The paired-samples t-test results for the total cognitive function score and the subdomains of cognitive function are presented in Table 13 and Table 14.

4.2.2. Stroop Test

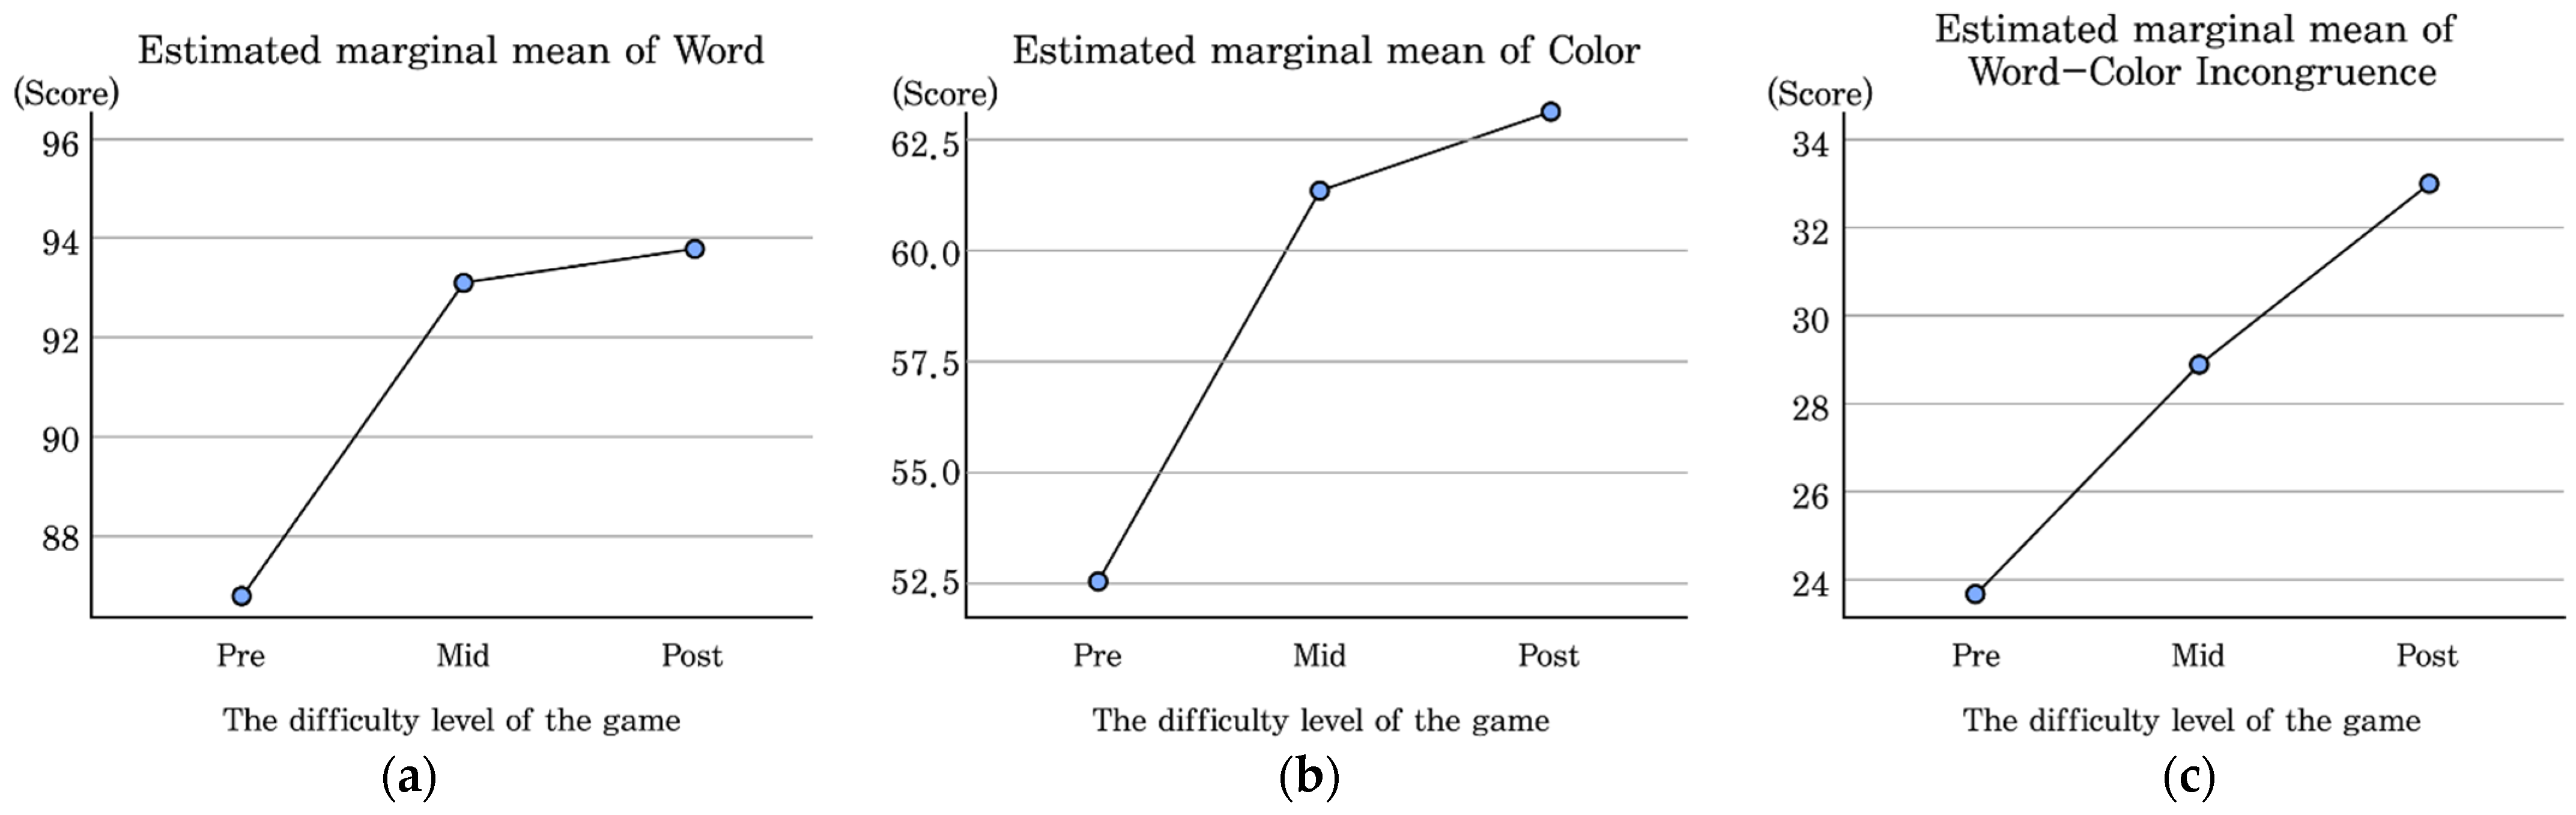
The analysis of the results of the Stroop task revealed consistent increases in post-test scores over pre-test scores across all conditions, including word reading, color naming, and the word–color incongruent condition, indicating improvements in overall cognitive processing speed and executive function. These changes were further supported by repeated-measures analysis of variance, which demonstrated statistically significant differences across time for word reading (p < 0.001, η2p = 0.378), color naming (p < 0.001, η2p = 0.455), and the incongruent condition (p < 0.001, η2p = 0.408).
The means and standard deviations for the Stroop task and the results of the repeated-measures ANOVA are presented in Table 15 and Table 16.
Notably, the largest magnitude of change was observed in the word–color incongruent condition, suggesting that the difficulty-adjustment components of the program were effective in stimulating cognitive abilities involving selective attention and inhibitory control. In other words, the progressive increases in game difficulty appear to have led to direct improvements in cognitive processing efficiency and executive function. A graphical representation of the Stroop Test results is presented in Figure 7.

4.2.3. Program Satisfaction

To assess participants’ overall satisfaction and perceptions of program usability, a separate satisfaction survey was administered at the conclusion of the program. The questionnaire consisted of 18 items in five evaluation domains: usability, usefulness, safety, sustainability, and open-ended questions. Of these, 16 items were multiple-choice questions scored on a 5-point Likert scale, while two items were open-ended questions designed to explore participants’ motivation for participation and factors influencing continued engagement. The survey items are presented in Table 17.
The results of the program satisfaction survey indicated a very high level of overall satisfaction, with a mean score of 4.66 on a 5-point Likert scale. Among the evaluation domains, safety received the highest rating (mean = 4.73), indicating that participants had strong confidence regarding safety throughout the program.
Analysis of the open-ended responses revealed that the most frequently reported motivation for participation was the expectation of improvements in physical and cognitive functions. In addition, the desire to experience a novel form of activity was identified as another important motivating factor. Factors contributing to sustained participation included the provision of three physical and cognitive assessments and the instructional approach of the program facilitator, both of which were perceived positively by the participants. The results of the program satisfaction evaluation are presented in Table 18.
When comparing participation experiences in individual and group exercise sessions, some participants reported occasionally skipping individual exercises due to fatigue, whereas they tended to engage more actively during group activities. One participant noted that “individual exercise allows for better concentration, while group activities are more enjoyable due to the added encouragement and sense of tension”. The average attendance rate across the program sessions was 78.7%, indicating a relatively high level of participation among the older adult participants.
These observations suggest that the provision of a safe program environment, active facilitation by instructors, social interaction among participants, and regular health-related feedback in integrated programs for older adults are key in higher program satisfaction and sustained participation.

5. Discussion

This study examined changes in physical and cognitive performance following participation in an offline dual-task-based integrated physical–cognitive program for older adults. The results suggest that within-group changes were observed in lower-extremity functional performance, dynamic balance, curved walking performance, and overall cognitive function over the intervention period. Falls in older adults often occur under dynamic conditions rather than being solely attributable to declines in lower-extremity function. Previous studies have suggested that dynamic balance, lower-extremity motor function, and cognitive ability are important factors associated with fall risk [41].
Compared with previous research that primarily focused on lower-extremity function or straight-line gait performance [36], the present study expanded the assessment of physical function to include dynamic balance and curved walking performance. These measures allowed for a broader examination of functional mobility and movement conditions more closely related to fall-risk-related performance. Improvements were observed across functional mobility measures, suggesting that participation in the program was associated with changes in multiple aspects of physical performance in older adults.
From a methodological perspective, OpenCap was used as a markerless motion capture tool to obtain additional kinematic information during task performance. By applying kinematic analysis to the FTSST, movement characteristics that are difficult to capture using conventional time-based measures alone could be examined across movement phases. The results showed no significant changes in overall joint RoM or most angular velocity parameters; however, knee joint angular velocity during the mid-phase of the movement increased significantly following the intervention period. These findings indicate that the observed changes were more apparent in phase-specific movement characteristics rather than in overall joint motion patterns. Although the changes were limited to specific parameters, kinematic analysis may provide complementary information on movement performance during functional tasks.
This pattern is consistent with previous studies suggesting that dual-task-based interventions may be associated with improvements in functional mobility and cognitive performance in older adults [42,43]. However, findings across studies have been variable depending on training protocols, task conditions, and measurement variables, and the present results should be interpreted with caution.
One possible explanation is that movement speed may be more sensitive to functional performance changes than other kinematic parameters. Velocity-related measures may more directly reflect changes in movement efficiency, whereas joint range of motion tends to remain relatively stable and may require longer intervention periods to show significant changes. Therefore, movement speed may serve as a more responsive indicator of short-term training-related adaptations in older adults.
With respect to cognitive performance, this study extended the assessment beyond the single cognitive screening measure (CIST) commonly used in previous research by additionally applying the Stroop Test. This approach allowed for changes in both general cognitive status and executive function-related processes such as cognitive processing speed and cognitive flexibility to be examined. Following the intervention period, changes were observed in executive function, memory, and cognitive processing speed. Because the present study employed a single-group design without a control condition, these findings should be interpreted as within-group changes over time rather than as effects attributable to the specific components of the intervention.
In this study, the CIST was administered at pre- and post-intervention, whereas the Stroop Test was assessed at multiple time points to capture short-term cognitive changes. This difference in measurement frequency reflects the distinct purposes and characteristics of each assessment tool. Accordingly, the results should be interpreted with consideration of these differences in assessment schedules.
Several contextual aspects of the program may have supported participant engagement, including the instructional approach of the facilitator, opportunities for feedback during training, progressive task structure, and group-based interaction. Participation continuity was higher in group-based activities than in individual exercises, suggesting that social interaction may play a role in supporting exercise engagement and structured participation in maintaining exercise engagement among older adults. This pattern was reflected in the program attendance rate, which averaged 78.7%, indicating relatively high adherence throughout the intervention period.
Several limitations should be acknowledged. First, the study included a relatively small sample size, which may limit the generalizability of the findings. It should be noted that the sample size in this study was determined based on feasibility considerations rather than an a priori statistical power calculation. The post hoc power estimation was conducted to provide additional context for interpreting the observed effects. However, this issue should be interpreted in the context of an intervention study involving older adults aged 65 years and above who were required to participate over an extended period. Recruiting and retaining older adults for sustained intervention studies is inherently challenging because of physical limitations, variability in health status, scheduling burden, and reduced willingness to engage in repeated assessments over time. In addition, the present study used a repeated-measures design that is statistically efficient for detecting within-subject change over time. The primary physical outcomes showed significant time effects with large observed effect sizes (FTSST: η2p = 0.395; FSST: η2p = 0.477; F8WT: η2p = 0.378), and an effect-size-based G*Power estimation suggested that approximately 9–10 participants would have been sufficient to detect the observed time effect under standard assumptions. Therefore, although the final sample of 19 participants was modest, it can be considered acceptable for detecting preliminary within-group changes. Nevertheless, future studies with larger and more diverse samples are needed to strengthen external validity and generalizability.
In addition, the higher proportion of female participants limited the ability to examine potential sex differences. Because the study employed a single-group design without a control condition, the observed changes should be interpreted as within-group changes over time rather than as effects attributable to the intervention. Furthermore, the findings may have been influenced by practice or familiarization effects associated with repeated assessments, as well as other uncontrolled factors. In particular, repeated exposure to cognitive assessments such as the Stroop Test may have contributed to practice-related improvements in cognitive performance. Although sufficient time intervals between assessments were maintained to minimize practice effects, the possibility of performance improvement due to repeated measurements cannot be completely excluded. Increased familiarity with task demands or response patterns may enable faster and more accurate responses, which could result in an increased number of correct responses and may be interpreted as an improvement in cognitive function. However, such changes may reflect task-related adaptation rather than true cognitive improvement. Therefore, the cognitive outcomes should be interpreted with caution.
Furthermore, multiple outcome variables were analyzed in this study, which may increase the risk of Type I errors associated with multiple statistical testing. The interpretation of kinematic variables derived from OpenCap may also have been influenced by variability in recording environments and individual movement strategies. Some variables did not meet normality assumptions, requiring cautious statistical interpretation.
A further limitation of this study concerns potential time-related confounding effects in the latter phase of the intervention. Although the total study schedule lasted 11 weeks, the active intervention period was 8 weeks, and this period included an unavoidable one-week interruption due to the temporary closure of the participating institution. After this interruption, the intervention resumed with an increased pad distance as part of the planned progression in task difficulty. Therefore, the relatively smaller improvement observed during the latter phase cannot be attributed solely to the increase in pad distance. It may also reflect the combined influence of interrupted training continuity, temporary detraining, repeated exposure, or other time-related factors. Accordingly, the independent effect of pad-distance progression cannot be fully disentangled in the present design. Future studies should adopt a more tightly controlled design to distinguish the specific contribution of task-difficulty progression from interruption-related or temporal confounding effects.
Despite these limitations, this study provides preliminary insights into changes in functional mobility and cognitive performance associated with participation in a gamification-based integrated physical–cognitive program for older adults. The integration of conventional functional assessments with kinematic analysis offers an additional perspective for examining movement characteristics during task performance and may support future research exploring quantitative movement analysis in exercise-based interventions for older adults.


6. Conclusions

This study suggests that functional changes in older adults may be more comprehensively captured by supplementing conventional time-based performance assessments with quantitative kinematic measures such as joint range of motion and phase-specific velocity during task execution. In particular, the markerless motion capture system OpenCap was used as a measurement tool to obtain additional kinematic information during functional task performance within a relatively simple and accessible measurement environment.
These findings suggest that such approaches may provide complementary information for evaluating functional movement characteristics in older adults and may inform future research on personalized exercise assessment and program design in digital healthcare contexts.
Furthermore, this study provides preliminary insights into the potential usefulness of a gamification-based integrated physical and cognitive program for older adults. Overall, the results suggest that combining conventional functional assessments with kinematic analysis tools may offer additional perspectives for evaluating intervention-related changes in functional mobility.
Supplementary Materials

The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/app16073133/s1, Table S1: Program Structure of the “Match It! Color Step” Program; Table S2: Session-Based Progression of Step-Pad Configuration and Stroop Task Difficulty.

Author Contributions

Conceptualization, J.-S.K. and J.-H.Y.; methodology, J.-S.K. and J.-H.Y.; software, J.-S.K.; validation, J.-S.K.; formal analysis, J.-S.K.; investigation, J.-S.K.; resources, J.-S.K.; data curation, J.-S.K.; writing—original draft preparation, J.-S.K.; writing—review and editing, J.-S.K. and J.-H.Y.; visualization, J.-S.K.; supervision, J.-H.Y.; project administration, J.-H.Y. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

This study was conducted after receiving approval (Institutional Review Board (IRB) No. KMU-202509-HR-504) from the Institutional Review Board (IRB) of Kookmin University to ensure ethical protection of the research subjects. Informed consent was obtained from all subjects involved in the study.

Informed Consent Statement

Written informed consent was obtained from all participants involved in the study.

Data Availability Statement

The raw data supporting this study are available from the authors and corresponding author upon request.

Acknowledgments

The authors would like to express their sincere gratitude to Jin-Ho Yim, the corresponding author, for his valuable support and guidance in this study.

Conflicts of Interest

The authors declare no conflicts of interest.

References

  1. Digital Times. Available online: https://www.dt.co.kr/article/12020737?ref=naver (accessed on 12 December 2025).
  2. Korea Disease Control and Prevention Agency. Available online: https://www.kdca.go.kr/kdca/2848/subview.do?enc=Zm5jdDF8QEB8JTJGYmJzJTJGa2RjYSUyRjQyJTJGMjE0OTI1JTJGYXJ0Y2xWaWV3LmRvJTNG (accessed on 14 December 2025).
  3. National Health Insurance Service. Available online: https://www.nhis.or.kr/magazin/149/html/sub1.html (accessed on 23 December 2025).
  4. Kim, S.J. Comparison of Muscle Contraction Onset Time During a Sit-to-Stand Task Among Young Adults, Healthy Older Adults, and Older Adults with a History of Falls. Master’s Thesis, Daegu University, Graduate School of Rehabilitation Science, Daegu, Republic of Korea, 2005. [Google Scholar]
  5. Oh, Y.-S.; Shin, Y.-J.; Han, K.-S. The effect of exercise program for physical fitness, mental health, and cognitive function in the elderly. Korean J. Growth Dev. 2007, 15, 295–302. [Google Scholar]
  6. Kang, B.R.; Park, S.H.; Kang, H.Y.; Ho, S.H.; Bae, Y. The effects of sequential dual-task training on cognitive and physical function in stroke patients: A case series study. J. Korean Soc. Neurocogn. Rehabil. 2023, 15, 47–55. [Google Scholar]
  7. Lee, H.K. Effects of an 8-Week Dual-Task Fall Prevention Exercise Program on Body Composition, Physical Function, Balance, Cognitive Function, and Psychosocial Characteristics in Older Adults. Doctoral Dissertation, Kyungnam University, Changwon, Republic of Korea, 2024. [Google Scholar]
  8. Lee, H.Y.; Hong, J.-H.; Song, W.-Y. Exercise motivations of regularly participating elderly individuals: Involvement, fun, and stress factors. Korean J. Sport Psychol. 2008, 19, 51–64. [Google Scholar]
  9. Chu, Y.-K.; Shon, J.-H. Effect of combined exercise program for 16 weeks on health-related physical fitness and depression in elderly women. J. Coach. Dev. 2012, 14, 105–114. [Google Scholar]
  10. Kim, J.; Lee, D.; Youn, S. Application of a dual-task-based physical activity program for improving cognitive function in older adults: An fNIRS study. J. Sport All 2025, 100, 289–298. [Google Scholar] [CrossRef] [Scilit]
  11. Na, B.-R.; Oh, B.-S. Aging and muscular strength in the lower limbs. Korean J. Res. Gerontol. 2020, 29, 1–24. [Google Scholar] [CrossRef] [Scilit]
  12. Kim, N.-I. The effect of complex exercise on physical performance and geriatric locomotive function scale in elderly with aging-induced sarcopenia. Korean J. Sport 2024, 22, 231–240. [Google Scholar] [CrossRef] [Scilit]
  13. Wang, H.; Huang, W.Y.; Zhao, Y. Efficacy of exercise on muscle function and physical performance in older adults with sarcopenia: An updated systematic review and meta-analysis. Int. J. Environ. Res. Public Health 2022, 19, 8212. [Google Scholar] [CrossRef] [Scilit]
  14. Choe, M.A.; Jeon, M.Y.; Choi, J.A. Effect of walk training on physical fitness for prevention in a home-bound elderly. J. Korean Acad. Nurs. 2000, 30, 1318–1332. [Google Scholar] [CrossRef] [Scilit]
  15. Jung, J.; Kim, J.M. The cognitive and affective characteristics of Korean older adults with subjective memory complaints. J. Korean Gerontol. Soc. 2015, 35, 835–851. [Google Scholar]
  16. Lee, H.W. Risk Factors for Cognitive Decline in Older Adults in Korea. Master’s Thesis, Kyung Hee University, Seoul, Republic of Korea, 2019. [Google Scholar]
  17. Clouston, S.A.; Brewster, P.; Kuh, D.; Richards, M.; Cooper, R.; Hardy, R.; Rubin, M.S.; Hofer, S.M. The dynamic relationship between physical function and cognition in longitudinal aging cohorts. Epidemiol. Rev. 2013, 35, 33–50. [Google Scholar] [CrossRef] [Scilit]
  18. Lee, B.; Park, J.-S.; Kim, N. The effect of physical activity programs on cognitive function, physical performance, gait, quality of life, and depression in the elderly with dementia. J. Spec. Educ. Rehabil. Sci. 2011, 50, 307–328. [Google Scholar]
  19. Song, C.; Kim, K. The effect of health promotion exercise on Alzheimer’s dementia-related factors and cognitive function in elderly women. Korean J. Sport Sci. 2018, 27, 1219–1228. [Google Scholar] [CrossRef] [Scilit]
  20. Nayak, A.; Alhasani, R.; Kanitkar, A.; Szturm, T. Dual-Task Training Program for Older Adults: Blending Gait, Visuomotor and Cognitive Training. Front. Netw. Physiol. 2021, 1, 736232. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Nascimento, M.d.M.; Maduro, P.A.; Rios, P.M.B.; Nascimento, L.d.S.; Silva, C.N.; Kliegel, M.; Ihle, A. The Effects of 12-Week Dual-Task Physical–Cognitive Training on Gait, Balance, Lower Extremity Muscle Strength, and Cognition in Older Adult Women: A Randomized Study. Int. J. Environ. Res. Public Health 2023, 20, 5498. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Chung, E.; Bok, J.; Yim, J. A study on the impact of stepping gamification on improving gait ability in elderly people. J. Ergon. Soc. Korea 2024, 43, 245–256. [Google Scholar] [CrossRef] [Scilit]
  23. Tae, J.; Lee, Y.; Choi, W. The relationship between aging and inhibition ability: Evidence from a web-based number Stroop task. Korean J. Cogn. Sci. 2025, 36, 1–20. [Google Scholar]
  24. Treiblmaier, H. Research commentary: Setting a definition, context, and theory-based research agenda for the gamification of non-gaming applications. AIS Trans. Hum.-Comput. Interact. 2018, 10, 129–163. [Google Scholar] [CrossRef] [Scilit]
  25. Kim, Y.J.; Kim, Y.; Kim, T. The impact of gamification strategies in fitness applications on user flow and continuous use intention. Korean J. Sport Manag. 2019, 24, 55–73. [Google Scholar] [CrossRef] [Scilit]
  26. Arufe-Giráldez, V.; Sanmiguel-Rodríguez, A.; Ramos-Álvarez, O.; Navarro-Patón, R. Gamification in physical education: A systematic review. Educ. Sci. 2022, 12, 540. [Google Scholar] [CrossRef] [Scilit]
  27. Guo, Y.; Yuan, T.; Yue, S. Designing personalized persuasive game elements for older adults in health apps. Appl. Sci. 2022, 12, 6271. [Google Scholar] [CrossRef] [Scilit]
  28. Park, Y.H.; Yun, R.J. Convergent gamification strategies to promote health behavior according to the tendency of goal achievement. J. Korean Soc. Sci. Arts 2019, 37, 141–155. [Google Scholar] [CrossRef] [Scilit]
  29. Chung, E.J. Research on Integrated Program Leveraging Gamification to Enhance Cognitive and Physical Fitness in the Elderly. Master’s Thesis, Kookmin University, Graduate School of Techno Design, Seoul, Republic of Korea, 2025. [Google Scholar]
  30. Seaborn, K.; Fels, D.I. Gamification in theory and action: A survey. Int. J. Hum.-Comput. Stud. 2015, 74, 14–31. [Google Scholar] [CrossRef] [Scilit]
  31. Han, A. A systematic literature review of research trends in domestic gamification. J. Korea Contents Assoc. 2018, 18, 566–578. [Google Scholar]
  32. Choi, M.; Park, B.; Koo, B.; Chae, J.; Kim, J. Human motion analysis based on a markerless motion capture using Kinect. In Proceedings of the Joint Conference of the Institute of Control, Robotics and Systems (ICROS); Institute of Control, Robotics and Systems: Seoul, Republic of Korea, July 2012; pp. 619–623. [Google Scholar]
  33. Yoo, Y.W. Validity of Lower-Limb Kinematic Variables Derived from a Markerless System During the Y-Balance Test and Comparison of Explanatory Power for Reach Distance. Master’s Thesis, Kookmin University, Graduate School, Seoul, Republic of Korea, 2022. [Google Scholar]
  34. Uhlrich, S.D.; Falisse, A.; Kidziński, Ł.; Muccini, J.; Ko, M.; Chaudhari, A.S.; Hicks, J.L.; Delp, S.L. OpenCap: Human movement dynamics from smartphone videos. PLoS Comput. Biol. 2023, 19, e1011462. [Google Scholar] [CrossRef] [Scilit]
  35. Kanko, R.M.; Laende, E.K.; Strutzenberger, G.; Brown, M.; Selbie, W.S.; DePaul, V.; Scott, S.H.; Deluzio, K.J. Assessment of spatiotemporal gait parameters using a deep-learning algorithm-based markerless motion capture system. J. Biomech. 2021, 122, 110414. [Google Scholar] [CrossRef] [Scilit]
  36. Chung, E.-J.; Yim, J.-H. An integrated program to improve cognitive and physical abilities in older people. Appl. Sci. 2025, 15, 2677. [Google Scholar] [CrossRef] [Scilit]
  37. Muñoz-Bermejo, L.; Adsuar, J.C.; Mendoza-Muñoz, M.; Barrios-Fernández, S.; Garcia-Gordillo, M.A.; Pérez-Gómez, J.; Carlos-Vivas, J. Test–retest reliability of the Five Times Sit-to-Stand Test (FTSST) in adults: A systematic review and meta-analysis. Biology 2021, 10, 510. [Google Scholar] [CrossRef] [Scilit]
  38. Park, C.S.; An, S.H. Test–retest reproducibility and smallest real difference of dynamic standing balance tests (F8WT, FSST, ST) in patients with stroke. J. Spec. Educ. Rehabil. Sci. 2024, 63, 197–211. [Google Scholar]
  39. Takahashi, S.; Grove, P.M. Use of the Stroop Test for sports psychology study: A crossover design research. Front. Psychol. 2020, 11, 614038. [Google Scholar] [CrossRef] [Scilit]
  40. Cerfoglio, S.; Lopes Storniolo, J.; de Borba, E.F.; Cavallari, P.; Galli, M.; Capodaglio, P.; Cimolin, V. Smartphone-Based Gait Analysis with OpenCap: A Narrative Review. Biomechanics 2025, 5, 88. [Google Scholar] [CrossRef] [Scilit]
  41. An, S.H.; Lee, B.K. The relationships among fall down, self-efficacy and the functional performance ability in stroke patients. J. Spec. Educ. Rehabil. Sci. 2011, 50, 269–288. [Google Scholar]
  42. Wollesen, B.; Voelcker-Rehage, C. Training effects on motor–cognitive dual-task performance in older adults. Eur. Rev. Aging Phys. Act. 2014, 11, 5–24. [Google Scholar] [CrossRef] [Scilit]
  43. Tait, J.L.; Duckham, R.L.; Milte, C.M.; Main, L.C.; Daly, R.M. Influence of sequential vs. simultaneous dual-task exercise training on cognitive function in older adults. Front. Aging Neurosci. 2017, 9, 368. [Google Scholar] [CrossRef] [Scilit]
Figure 1. Stepping-pad configuration for the Stroop Stepping Game.
Applsci 16 03133 g001
Figure 2. Physical and Cognitive Research Model. Note: ‘+’ indicates the combination of multiple components.
Applsci 16 03133 g002
Figure 3. “Match It!” Color-Step game (individual mode) (a), “Match It!” Color-Step game (team-based mode) (b).
Applsci 16 03133 g003
Figure 4. Estimated marginal averages of FTSST (a), FSST (b), F8WT (c).
Applsci 16 03133 g004
Figure 5. Pre–post knee joint angles (a), knee joint angles at 25% (b), 50% (c), and 75% (d) of the movement phase.
Applsci 16 03133 g005
Figure 6. Pre–post intervention angular velocity at the 25% (a), 50% (b), and 75% (c) phases.
Applsci 16 03133 g006
Figure 7. Estimated marginal averages of Word (a), Color (b), and Word–Color Incongruence (c).
Applsci 16 03133 g007
Table 1. Characteristics of the Participants (N = 19).
MeasureCharacteristicNumber of
Participants (n)
GenderMale4
Female15
Education LevelElementary school3
Middle school5
High school7
University degree4
Age60s5
70s13
80s1
Cognitive Status (CIST)Normal16
Suspected cognitive decline3
MeasureMean ± SD
Age (years)73.68 ± 2.76
Height (cm)157.21 ± 5.09
Weight (kg)58.09 ± 8.40
BMI (kg/m2)23.46 ± 2.79
Skeletal Muscle Mass (kg)21.36 ± 3.22
Body Fat Mass (kg)18.07 ± 4.48
Body Fat Percentage (%)30.89 ± 4.85
Table 2. Program Overview.
CategoryDescription
Program TitleMatch It! Color Step
Participants19 Participants
Period25 August 2025–7 November 2025 (11 weeks)
SessionsTwice per week, total of 20 sessions
(1 program orientation and practice game, 16 main program sessions, and 3 assessment sessions)
Session DurationAbout 50–55 min
Table 3. Program Components and Materials.
TitleGame ProcedureGame Equipment
Match It! Color StepApplsci 16 03133 i001Applsci 16 03133 i002
Circular Marker Set Made of SEBS Material, 24 cm Diameter
Styrofoam Rings
Table 4. Layout of Individual and Team-Based Game Operations.
Game Layout Diagram
Individual ModeTeam-Based Mode
Applsci 16 03133 i003Applsci 16 03133 i004
Table 5. Gamification Strategies Applied in the Program.
Gamification Strategies
CompetitionCompetition with other teams, individual leaderboards
AchievementAttendance scoreboard, progression of game difficulty, sharing of task performance
RewardsThree rounds of physical and cognitive assessments, program completion certificate, gift rewards
Social InteractionCommunity building and interaction among program participants
Table 6. Assessment Tools and Measurement Timeline for Physical and Cognitive Outcomes.
MeasureAssessment ToolPreMidPost
PhysicalFTSSTOOO
FSSTOOO
F8WTOOO
OpenCapOOO
CognitiveCISTO-O
Stroop TestOOO
Program Satisfaction --O
Note: ‘O’ indicates that the assessment was conducted at the corresponding time point; ‘-‘ indicates that the assessment was not conducted.
Table 7. Changes in the Physical Performance of Participants (N = 19).
VariablePreMidPost
Body weight (kg)58.09 ± 8.4 58.16 ± 8.2457.72 ± 8.51
BMI (kg/m2)23.46 ± 2.7923.37 ± 2.7123.3 ± 2.88
Skeletal muscle mass (kg)21.36 ± 3.2221.57 ± 3.1521.22 ± 2.91
Body fat mass (kg)18.07 ± 4.4817.7 ± 4.5617.94 ± 5.1
Body fat percentage (%)30.89 ± 4.8530.25 ± 5.0930.67 ± 5.52
Note: Values are presented as mean ± standard deviation (SD).
Table 8. Means and Standard Deviations of FTSST, FSST, and F8WT Scores (N = 19).
VariableMeasurePreMidPost
Lower-extremity muscle strengthFTSST 9.99 ± 2.388.24 ± 1.698.48 ± 1.76
Dynamic balance abilityFSST 10.19 ± 2.198.37 ± 1.238.13 ± 1.38
Curved walking abilityF8WT 6.63 ± 1.125.86 ± 1.085.93 ±1.3
Note: Values are presented as mean ± standard deviation (SD).
Table 9. Repeated-Measures ANOVA Results for FTSST, FSST, and F8WT Scores (N = 19).
VariableType III SSdfMSFpη2p
FTSST 134.2451.52922.40211.754<0.001 ***0.395
FSST 148.3111.47332.79116.429<0.001 ***0.477
F8WT6.867 23.43410.938<0.001 ***0.378
*** p < 0.001. 1 Greenhouse–Geisser corrected values are reported when the assumption of sphericity was violated according to Mauchly’s test.
Table 10. Shapiro–Wilk Tests of Normality for Joint Angles and Angular Velocities (N = 19).
VariablePrePost
RoM0.004 ** 0.778
Vel RoM 25%0.4040.775
Vel time 25%0.3770.415
Vel RoM 50%0.3050.384
Vel time 50%0.9200.632
Vel RoM 75%0.9020.047 *
Vel time 75%0.026 *0.406
* p < 0.05, ** p < 0.01.
Table 11. Paired-Samples T-Tests for Joint Angles and Angular Velocities at 25% and 50% Phases (N = 19).
VariablePrePosttdfpCohen’s d
Vel RoM 25%211.35 ± 63.05 217.53 ± 56.19−0.378180.7100.087
Vel time: 25%133.58 ± 87.13140.46 ± 68.23−0.411180.6860.094
Vel RoM 50%210.33 ± 50.74210.59 ± 56.76−0.023180.9820.01
Vel time: 50%124.07 ± 60.9158.36 ± 61.05−2.605180.018 *0.6
* p < 0.05.
Table 12. Wilcoxon Signed-Rank Tests for Overall Joint Angles and for Joint Angles and Angular Velocities at the 75% Phase (N = 19).
VariablePrePostZpCohen’s d
RoM81.86 ± 12.82 83.29 ± 8.65−0.4830.6290.102
Vel_RoM_75%125.12± 29.39141.93 ± 33.33−1.8110.070.495
Vel_time_75%68.94 ± 52.5572.33 ± 53.35−0.1610.8720.05
Table 13. Paired-Samples t-Test Results for Pre–Post Cognitive Function (N = 19).
VariableMeasurePrePosttpCohen’s d
Cognitive FunctionCIST25.47 ± 4.228 ± 1.91−2.8080.012 *0.64
* p < 0.05.
Table 14. Paired-Samples t-Test Results for Subdomains of Cognitive Function (N = 19).
VariablePrePosttpCohen’s d
Immediate Memory4.89 ± 0.45 5.0 ± 0−1.000.3310.23
Attention2.52 ± 0.612.57 ± 0.5−0.3250.7490.08
Visuospatial Ability1.84 ± 0.51.68 ± 0.670.9000.3800.21
Executive Function4.31 ± 1.05.36 ± 0.89−5.410<0.001 ***1.24
Memory Recall8.21 ± 2.659.68 ± 0.89−2.3840.028 *0.55
Language Ability3.63 ± 0.593.68 ± 0.47−0.5670.5780.13
* p < 0.05, *** p < 0.001.
Table 15. Means and Standard Deviations of the Stroop Test (N = 19).
VariablePreMidPost
Word86.89 ± 11.3793.95 ± 8.9394.74 ± 9.42
Color52.42 ± 13.0761.32 ± 1262.11 ± 12.8
Word–Color Incongruent23.68 ± 7.5928.84 ± 9.3332.95 ± 11.28
Note: Values are presented as mean ± standard deviation (SD).
Table 16. Repeated-Measures ANOVA Results for the Stroop Test (N = 19).
VariableType III SSdfMSFpη2p
Word708.4562354.22810.960<0.001 ***0.378
Color1244.3162622.15815.028<0.001 ***0.455
Word–Color Incongruent818.6672409.33312.39<0.001 ***0.408
*** p < 0.001.
Table 17. Structure of the Program Survey Items.
Survey ItemsItem DescriptionNumber of
Questionnaire Items
UsabilityItems assessing program pace, comprehensibility, level of game difficulty,
and the facilitator’s program delivery competence
10
UsefulnessItems comparing perceived improvements in physical and
cognitive functions before and after the program
3
SafetyItems evaluating overall program safety1
SustainabilityItems assessing willingness to participate in other programs and intention to recommend the program to others2
Open-ended QuestionsOpen-ended items exploring motivation for program participation and factors influencing continued engagement2
Note: Items were scored on a 5-point Likert scale (except for open-ended items).
Table 18. Results of the Program Satisfaction Evaluation (N = 19).
Survey ItemsPost
Usability4.64 ± 0.63
Usefulness4.7 ± 0.56
Safety4.73 ± 0.45
Sustainability4.64 ± 0.62
Total4.66
Note: Values are presented as mean ± standard deviation (SD), except for the total score.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.