


Abstract
Background: Total hip arthroplasty (THA) is one of the most effective treatments for end-stage hip joint disease. Two-dimensional (2D) templating represents the most widely used method for preoperative planning in clinical practice. Patient characteristics and comorbidities may further influence and complicate radiographic templating. The present study aimed to evaluate the role of comorbidities in influencing the accuracy of 2D digital preoperative planning in primary cementless THA. Methods: In this prospective observational study, all patients underwent standardized anteroposterior pelvic radiographs, and a digital templating was performed using digital software. Patient demographic characteristics, such as age, sex, BMI, and comorbidities, were extracted and all the patients were divided into matched and mismatched group for the femoral stem, femoral head, and acetabular cup. Results: The final sample consisted of 71 patients with 44 (62%) female and 27 (38%) male patients, averaging 69.8 ± 10.6 years at surgery. For the femoral stem, no statistically significant differences were found between the two groups according to comorbidities. For the femoral head, 12.5% and 50% of the patients had osteoporosis in the matched group and mismatched group, respectively (p-value = 0.002). For the acetabular cup, 18.4% and 40.9% of the patients had osteoporosis in the matched and mismatched groups, respectively (p-value = 0.043). Conclusions: Two-dimensional digital templating is a reliable technique for preoperative planning in primary cementless THA. Osteoporosis significantly influences templating accuracy, often resulting in component oversizing.
1. Introduction
Total hip arthroplasty (THA) is one of the most effective treatments for end-stage hip joint disease, including hip osteoarthritis, femoral neck fractures, and various degenerative conditions affecting hip function [1]. Despite these excellent results, after THA, from 7 to 15% of patients report dissatisfaction [2]. Achieving optimal surgical outcomes relies heavily on preoperative planning to restore proper biomechanics, such as leg length, femoral offset, and center of rotation, while preventing complications and the need for revision surgery [3]. Two-dimensional (2D) templating using standard radiographs represents the most widely used method for preoperative planning in routine clinical practice due to its cost-efficiency, accessibility, and low radiation dose [3,4,5,6] despite its inherent limitations, such as magnification errors, variations in patient positioning, and interobserver variability. Several systematic reviews and meta-analyses demonstrated that three-dimensional (3D) CT-based planning methods offer superior accuracy in predicting component size and alignment compared to conventional 2D templating [1,7,8,9]. Moreover, 3D planning showed significantly greater accuracy than 2D digital templating for short-stem implants, although performance was comparable for straight stems [10]. Despite its limitations, 2D templating is still commonly used and has shown acceptable performance in clinical settings, with approximately 85–90% of cases falling within ±1 size of the actual component implanted [11,12,13]. However, patient-specific variables and technical factors continue to affect its performance: software quality, surgeon experience, and calibration techniques influence the reliability of 2D planning [14,15,16].
In addition to these technical aspects, emerging evidence suggests that patient characteristics and comorbidities may further influence the bone morphology, anatomical landmarks, and radiological appearance of the hip, complicating radiographic templating. Body Mass Index (BMI), patient sex, and radiographic calibration are known to affect magnification and templating accuracy: obese patients tend to have a higher radiographic magnification factor, potentially leading to oversizing [17,18]. Prospective studies have shown that high BMI does not affect implant size templating but may reduce the accuracy in some parameters, such as leg length discrepancy or femoral offset [19]. Osteoporosis, characterized by reduced bone mineral density (BMD) and microarchitectural deterioration, may affect cortical definition and radiographic contrast, thus complicating anatomical landmark identification [20], and these changes may lead to underestimation of implant size in preoperative planning [21,22]. Patients affected by Chronic Kidney Disease often develop CKD-related mineral and bone disorder (CKD-MBD), a syndrome characterized by altered bone turnover, mineralization, and strength [23]. This condition appears radiographically as low bone density or cortical thinning, which may interfere with the accurate measurement of femoral or acetabular dimensions, although targeted studies in THA templating are lacking [24]. Type 2 Diabetes Mellitus (DM) is associated with impaired bone microarchitecture despite often normal BMD values, a phenomenon known as “diabetic bone disease” [25,26]. This hidden bone fragility may affect load distribution, potentially requiring larger components intraoperatively than what preoperative planning anticipates. Lastly, chronic inflammatory states from autoimmune, endocrine, or neurologic diseases may indirectly affect bone and muscle quality and joint morphology, though direct correlations with templating discrepancies remain underexplored [27,28].
Importantly, complex preoperative anatomical conditions can reduce templating accuracy, such as in patients with hip dysplasia. In these cases, the concordance between preoperative templates and implanted components was about 38–43%, demonstrating that comorbidities and anatomical alteration may cause error in 2D templating [29].
Even if the BMI, radiographic technique, and operator experience have been extensively studied, there is still limited research specifically assessing how individual comorbidities affect the match between preoperative 2D digital planning and the final implants used intraoperatively. Understanding this gap is crucial to overcoming the mismatch and reducing the risk of suboptimal component selection, longer surgical time, increased inventory utilization, and potentially compromised patient outcomes.
The present prospective study aimed to evaluate the role of comorbidities in influencing the accuracy of 2D digital preoperative planning in primary cementless THA. We hypothesized that the presence of comorbidities may impact templating accuracy.
2. Materials and Methods
2.1. Study Design
This prospective observational study was conducted following the guidelines defined by the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) guidelines and checklist. The study protocol was approved by the Local Ethics Committee and the research was conducted in compliance with the Declaration of Helsinki. All participants provided informed consent before the beginning of the study.
2.2. Participants
The study was conducted on a cohort of patients who underwent THA at the Department of Orthopaedic and Trauma Surgery of the Magna Græcia University and Renato Dulbecco University Hospital in Catanzaro, Italy, between June 2022 and February 2024. The inclusion criteria were (1) age ≥ 18 years; (2) availability of standard anteroposterior pelvic radiographs with proper calibration; (3) preoperative 2D templating performed using the digital software TraumaCad® (version 2.5, BrainLab Inc., Westchester, IL, USA); (4) primary, elective, and unilateral cementless THA; and (5) availability of complete comorbidity records. Subjects were excluded in cases of (1) revision THA; (2) simultaneous bilateral THA; (3) previous proximal femoral or acetabular surgery; or (4) incomplete radiographic or clinical records.
2.3. Preoperative Templating Protocol
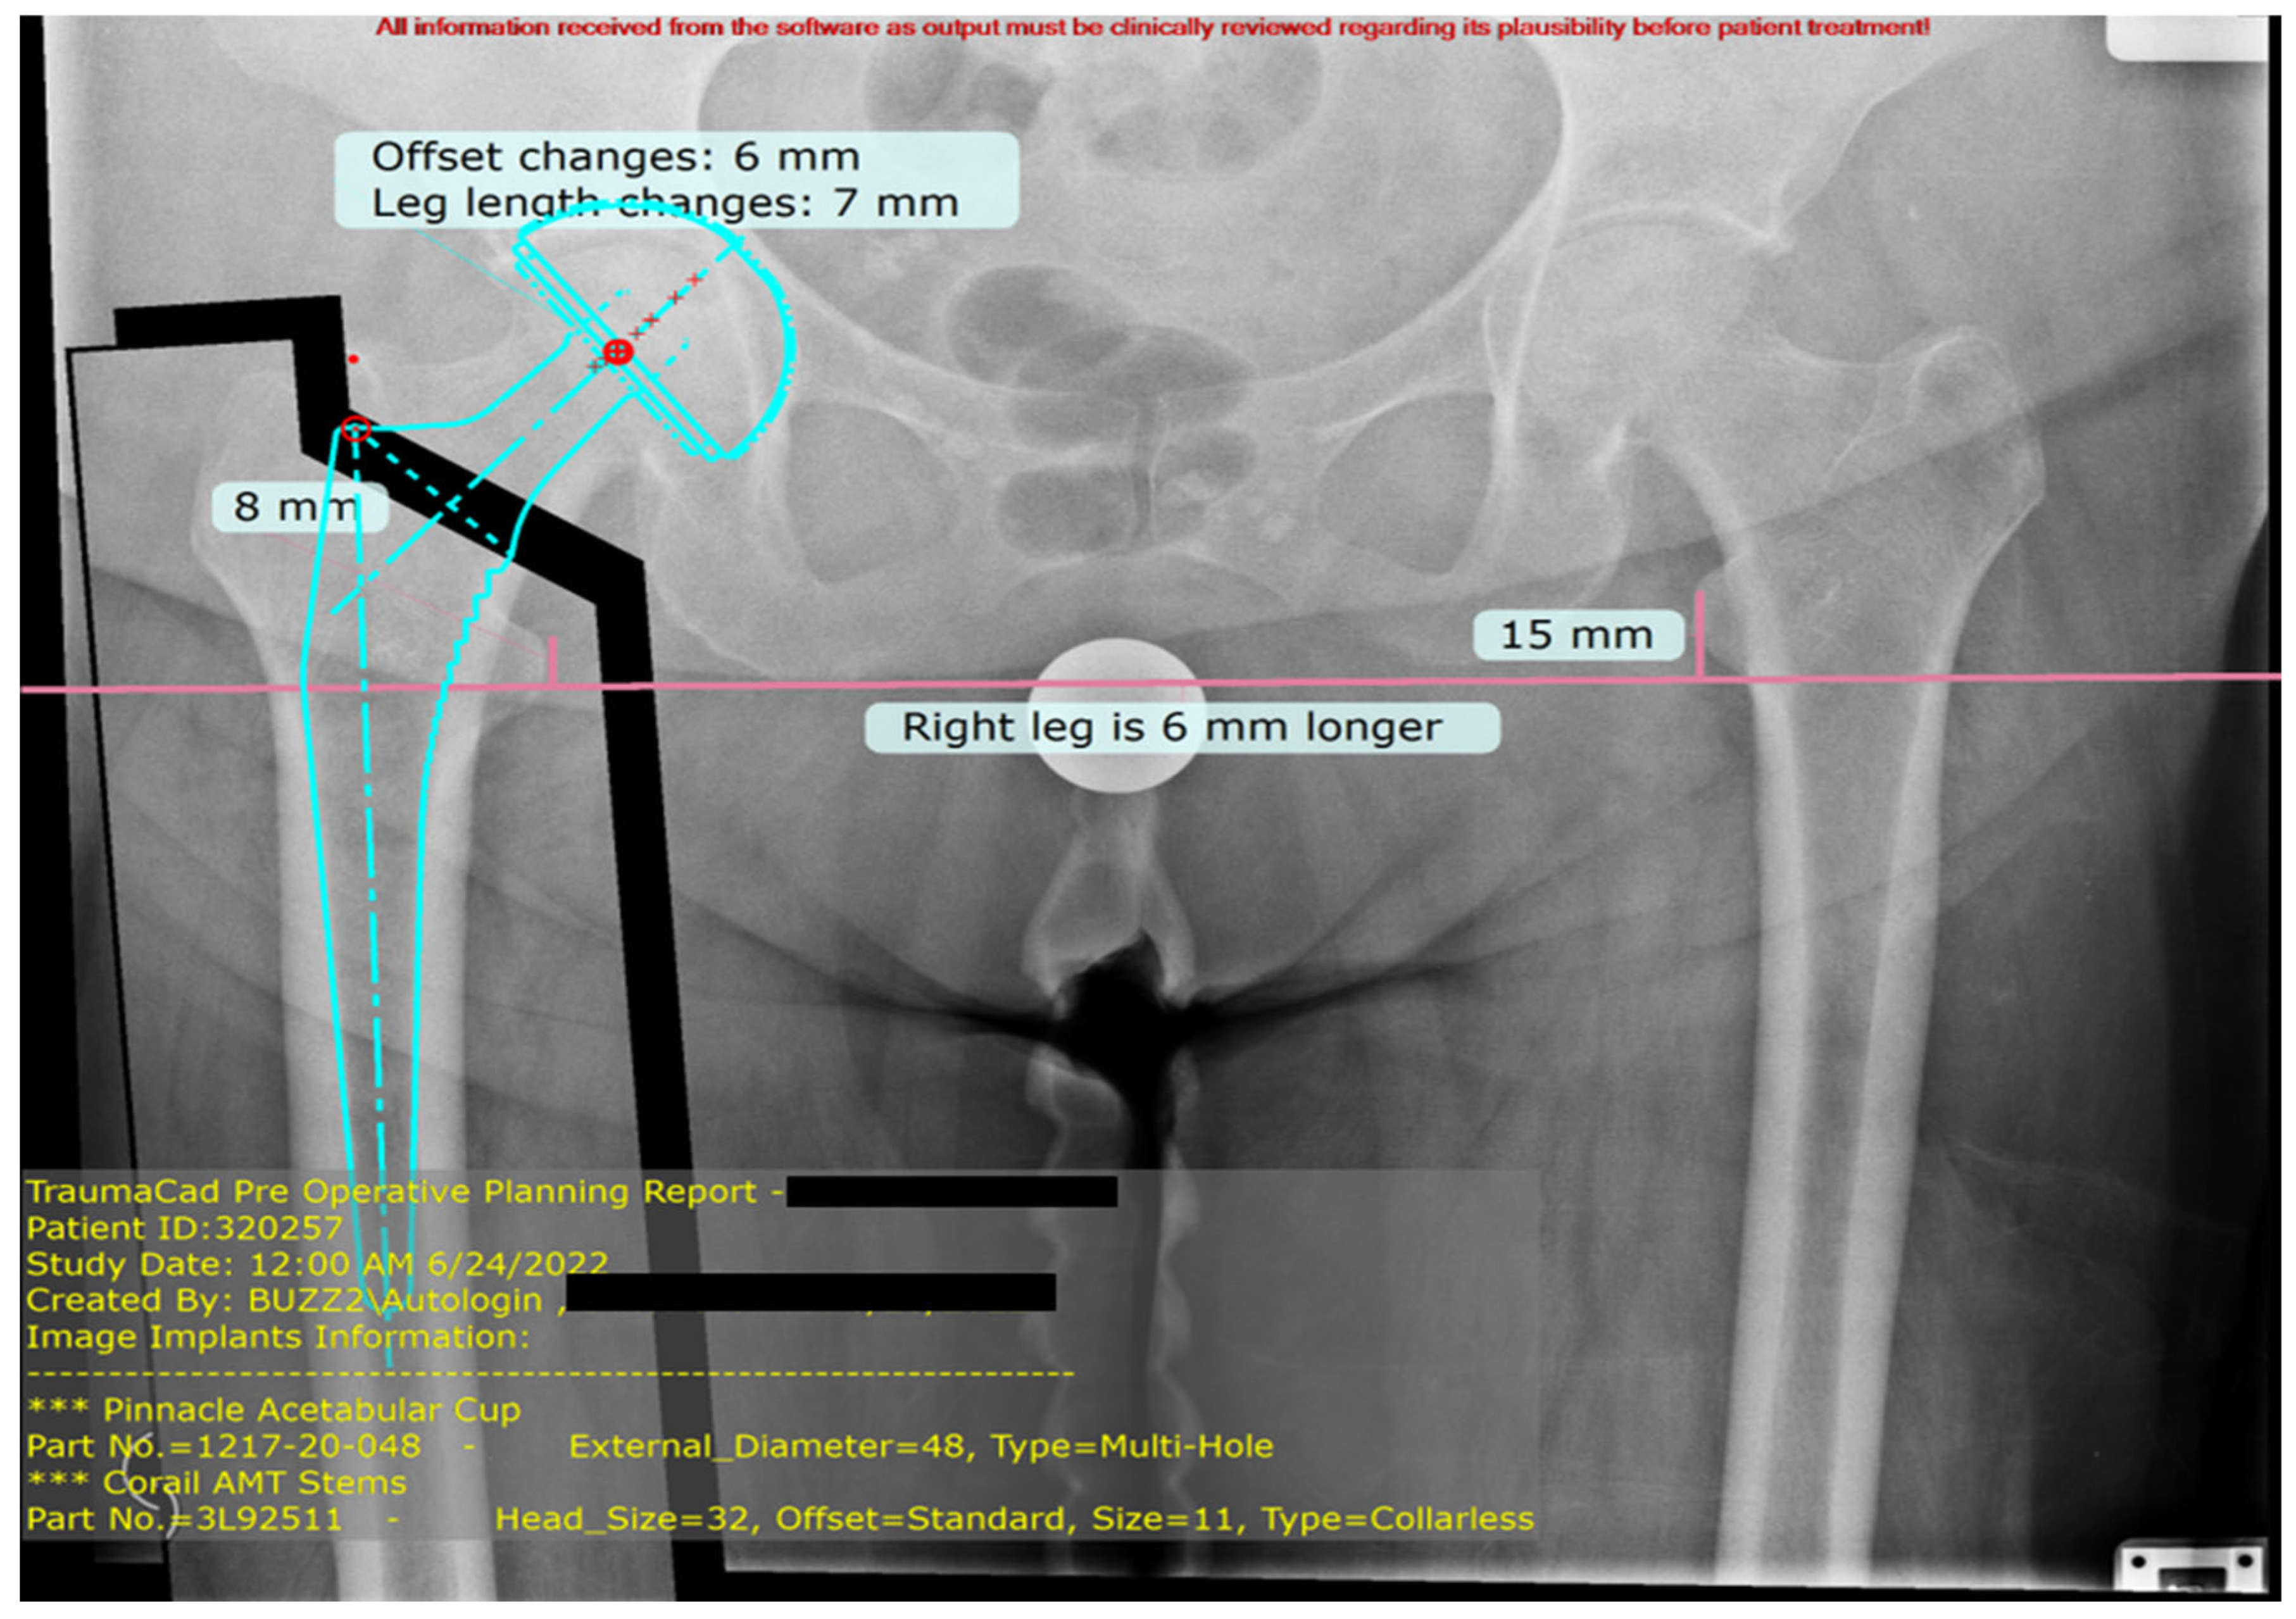
All patients underwent standardized anteroposterior pelvic radiographs. Radiographs were taken with the patient in a standing position and with both legs in 15° internal rotation. The beam was centered on the symphysis pubis. Digital templating was performed using the digital software TraumaCad® (version 2.5, BrainLab Inc., Westchester, IL, USA) by two independent experienced orthopedic surgeons to assess the interobserver reliability (Figure 1).
Figure 1.
Digital templating of total hip arthroplasty.
The same surgeons performed the digital template again after two weeks to assess the intraobserver reliability. Calibration was standardized using a metal reference sphere with a diameter of 25 mm. The teardrop is created by the superposition of the most distal part of the medial wall of the acetabulum and the tip of the anterior and posterior points of the acetabulum; the acetabular roof and the teardrop are considered reliable radiographic landmarks for the pelvic side. The anatomical landmarks were (1) hip rotation center; (2) longitudinal axis of the proximal femur; (3) femoral offset; (4) acetabular offset; (5) hip length; and (6) leg length discrepancy (LLD), calculated as the difference between the distances from the radiographic drop and the lesser trochanter on both sides. The appropriate stem size was selected by choosing the stem that filled the intramedullary canal. The acetabular component was placed at the floor of the acetabulum, as this was the intended final position intraoperatively [3].
Component sizing was performed for the femoral stem, femoral head, and acetabular cup. The planned sizes were recorded and later compared to the implanted sizes at surgery.
2.4. Surgical Technique
All procedures were performed by a single experienced orthopedic surgeon who was not blinded to the template and used a standardized posterior approach [30]. All patients were placed in the lateral decubitus position, which was carefully checked to ensure the pelvis was perpendicular to the ground. Deep vein thrombosis (DVT) prophylaxis was carried out by administration of low-molecular-weight heparin [31], antibiotic prophylaxis was administered intravenously as recommended [32], and in the absence of contraindications, either spinal or epidural anesthesia was performed for all procedures. All THAs were performed using a cementless, proximally hydroxyapatite-coated, tapered stem with a cementless, hemispherical acetabular shell, a ceramic femoral head, and a polyethylene acetabular liner (Corail® femoral stems and Pinnacle® acetabular component; DePuy International Ltd., Leeds, UK). Intraoperatively, the template was used as a guide, and the surgeon chose the final prosthesis with complete autonomy. Fluoroscopy was not used intraoperatively [33].
2.5. Comorbidities and Clinical Variables
Patient demographic characteristics, such as age, sex, BMI, and comorbidities, were extracted from clinical records. The comorbidities considered were osteoporosis, endocrine diseases (e.g., hypothyroidism), rheumatic diseases (e.g., psoriasis, rheumatoid arthritis), neurological disorders (e.g., Parkinson’s disease, myasthenia gravis), CKD, and DM. Each comorbidity was defined as present or absent and analyzed for its association with planning-to-implant mismatch.
2.6. Outcome Measures
The primary outcome was the concordance rate between the preoperatively planned and the implanted component sizes. Secondary outcomes included the average deviation (in sizes) between planned and implanted components, the association between specific comorbidities and mismatch rates, and the direction of mismatch (i.e., oversizing or undersizing relative to planning).
2.7. Statistical Analysis
All data were measured, collected, and reported to one decimal accuracy. The mean, standard deviation, and range were noted for the continuous variables, and counts for the categorical variables were recorded. The distribution of the numeric samples was assessed by the Kolmogorov–Smirnov normality test. Based on this preliminary analysis, parametric tests were adopted. For each of the three prosthetic components (femoral stem, femoral head, and acetabular cup), patients were grouped into matched groups when the implanted component size was identical to the preoperative plan and mismatched groups when the implanted component differed from the planned size. The variation (in sizes) between planned and implanted components was recorded for each patient. To evaluate the significance of differences between preoperative and postoperative values and between the groups, a two-tailed paired and unpaired Student’s t-test was performed, respectively. The differences for categorical variables were tested by the χ2 (chi-squared) test. Inter- and intraobserver agreements for prosthetic component sizes were evaluated by the intraclass correlation coefficient (ICC) 2-by-2 with a 95% confidence interval [34]. The power of ICC values was interpreted according to the Landis and Koch classification as follows [35]: no agreement to slight agreement, <0.20; fair agreement, 0.21 to 0.40; moderate agreement, 0.41 to 0.60; substantial agreement, 0.61 to 0.80; and almost perfect agreement, 0.81 to 1.00.
IBM SPSS Statistics software (version 26, IBM Corp., Armonk, NY, USA) and G*Power (version 3.1.9.2, Institut für Experimentelle Psychologie, Heinrich Heine Universität, Düsseldorf, Germany) were used for database construction and statistical analysis. A p-value of less than 0.05 was considered significant.
3. Results
The demographic characteristics of the included patients and the average sizes of the templated and implanted prosthetic components are summarized in Table 1.
Table 1.
Characteristics of the included patients.
The final sample consisted of 71 patients. There were 44 (62%) female and 27 (38%) male patients, averaging 69.8 ± 10.6 (range 31–88) years at surgery. The mean Body Mass Index (BMI) was 28.5 ± 4.4 kg/m2 (range 20–41). Considering comorbidities: 16 (22.5%) patients had osteoporosis, 12 (16.9%) endocrine diseases, 8 (11.3%) rheumatic disease, 4 (5.6%) neurological diseases, 6 (8.5%) CKD, and 15 (21.1%) DM. The analysis of inter- and intraobserver reliability showed strong agreement with an ICC > 0.81 for all the prosthetic component sizes evaluated, demonstrating that the data were reproducible. The ICCs of the interobserver reliability were 0.821, 0.865, and 0.887 for femoral stem, femoral head, and acetabular cup, respectively. The ICCs of the intraobserver reliability were 0.931, 0.901, and 0.943 for femoral stem, femoral head, and acetabular cup, respectively.
For each of the three prosthetic components (femoral stem, femoral head, and acetabular cup), patients were grouped into a matched group when the implanted component size was identical to the preoperative plan and a mismatched group when the implanted component differed from the planned size. For the femoral stem, a total of 49 (69%) cases matched the preoperative planning.
Table 2 showed the differences between the two groups according to comorbidities: no statistically significant differences were found.
Table 2.
Planning adherence and comorbidities for the femoral stem size.
For the femoral head, a total of 40 (71.4%) cases matched with the preoperative planning.
Table 3 showed the differences between the two groups according to comorbidities: 12.5% and 50% of the patients had osteoporosis in the matched group and mismatched group, respectively (p-value = 0.002).
Table 3.
Planning adherence and comorbidities for the femoral head size.
Considering the results, we also analyzed how much the femoral head varied from planning to final implantation in patients with mismatch and with osteoporosis, finding that the implanted head was 1 ± 0.9 size larger than planned.
For the acetabular cup, a total of 49 (69%) cases matched with the preoperative planning.
Table 4 showed the differences between the two groups according to comorbidities: 18.4% and 40.9% of the patients had osteoporosis in the matched and mismatched groups, respectively (p-value = 0.043). Considering the results, we analyzed how much the acetabular cup varied from planning to final implantation in patients with mismatch and with osteoporosis, finding that the acetabular cup was 1.3 ± 1.7 sizes larger than planned.
Table 4.
Planning adherence and comorbidities for the acetabular cup size.
4. Discussion
The primary objective of the present prospective observational study was to evaluate the role of comorbidities, such as osteoporosis, AH, CKD, and DM, in influencing the accuracy of 2D digital preoperative planning in primary cementless THA in terms of the concordance between the preoperatively planned and the implanted component size. Our findings showed that systemic comorbidities, specifically osteoporosis, were significantly associated with a mismatch between preoperative 2D templated sizes and final components implanted in THA, with a consistent trend toward oversizing. These observations suggest that patients with compromised bone quality may exhibit features that lead surgeons to select larger implant sizes intraoperatively.
Overall, the results of our study showed that 2D digital templating is a reliable technique for preoperative planning with implanted component size within one or two sizes of template [36]. In this context, evidence suggested there is no compromise in the post-operative outcome when selecting intraoperative implants at one or two size differences from the template [19].
This is consistent with Almeida et al.; this study reported that 2D radiographs provide only one view of the pelvis and femur, necessarily subjecting their dimensional data to loss compared with CT-based planning. Three-dimensional CT templating could, in fact, achieve better accuracy, particularly in difficult anatomies, by eschewing the geometric restrictions of 2D imaging. However, CT-based protocols have attendant increased radiation exposure, expense, and restricted routine practice in daily clinical life. For these reasons, despite having inherent dimensional fallibility, 2D digital templating is the most widely used and clinically practical approach. In carefully chosen high-risk cases, such as severe osteoporosis or complex deformity, CT-based or 3D planning may have payoff, but use should be balanced against feasibility and risk–benefit [37].
While most prior studies focused on the technical accuracy of 2D templating and variables such as BMI and surgeon experience [8,13], few have evaluated the specific role of comorbidities. Our results align with the perspective that osteoporosis negatively influences anatomical landmark clarity and may lead to templating underestimation [38,39]. It should be considered that people living with osteoporosis present an impaired global functioning, particularly relating to physical, psychological, and social aspects, with the highest risk of obesity, and sedentary lifestyle [40]. This is also in accord with evidence linking low bone mineral density to periprosthetic complications and increased revision risk [3,4,21,39,41]. Several studies have investigated the influence of osteoporosis on preoperative planning. A study by Sariali et al. [42] found that 3D templating provides higher accuracy in comparison to 2D templating, particularly when bone quality is compromised, such as in osteoporosis. Similarly, Pansard et al. demonstrated that a 2D template oversized the implant in osteoporotic patients [43]. Ding et al. [1] found that as the quality of the bone mineral density decreased, the accuracy of the templating decreased. The same authors also found that the rate of agreement for patients with excellent bone quality was higher than that for patients with osteoporosis.
Beyond the mechanical and radiographic aspects, it is important to recognize the underlying pathophysiological mechanisms by which comorbidities may influence preoperative planning. In osteoporosis, the progressive deterioration of trabecular architecture and cortical thinning results in reduced radiographic contrast between bone and soft tissue, making it more challenging to accurately delineate anatomical landmarks used during templating. In addition, age-related degenerative changes such as osteophyte formation or acetabular protrusion—more common in osteoporotic patients—can further distort the native anatomy and complicate the templating process.
These findings have direct implications for surgical planning. Surgeons should add a study of bony quality, such as DEXA. Anticipating potential oversizing intraoperatively allows an appropriate inventory preparation and reduces delay. Moreover, integrating comorbidity profiles with 2D planning can enhance implant section accuracy and reduce complications.
The tendency toward oversizing in patients with osteoporosis could have several consequences. First, in the acetabular component, excessive reaming to accommodate a larger cup may compromise bone stock and hinder future revision procedures. Second, anticipating larger component needs may improve implant availability and reduce intraoperative delays. Third, underappreciating bone quality may lead to improper implant fit and require intraoperative adjustments. Lastly, osteoporotic patients mismatched to larger implants might face an increased risk of periprosthetic complications [44,45]; moreover, osteoporosis is associated with almost double the risk of revision due to periprosthetic fracture in 5 years [46]. Therefore, integrating preoperative bone assessment (e.g., DEXA, trabecular structure scoring) and a critical evaluation of systemic comorbidity profiles may enhance templating accuracy and planning.
To the best of our knowledge, this study is the first to directly assess the influence of systemic comorbidities on 2D digital templating accuracy in THA, highlighting clinically relevant associations. The methodology was reliable: two independent trained orthopedic surgeons performed the digital templating, and high inter- and intraobserver reliability was observed for all the prosthetic component sizes evaluated. This finding emphasizes that, despite the limitation of 2D templating, the method provides reproducible and consistent results across observers, supporting its validity in clinical practice. The use of real-world clinical data and the inclusion of multiple comorbidities provide a comprehensive analysis. However, it is not free from limitations. First, the small sample size limits statistical power for less common conditions. Moreover, the absence of objective bone density measurements (e.g., DEXA) and lack of data on medications (such as bisphosphonates, denosumab, dual-action or anabolic drugs) are central constraints [47]. Additionally, the single surgeon and the single-center setting may limit generalizability. Moreover, the type of diagnosis, the single posterior surgical approach adopted, and the single type of cementless implant used may have influenced the results.
Given the influence of systemic health on local bone characteristics, a more comprehensive preoperative evaluation may be necessary. In selected cases—especially elderly patients or those with known osteoporosis—a multidisciplinary assessment involving orthopedics, internal medicine, and bone metabolism specialists can help develop a more detailed understanding of surgical risks and planning requirements. Preoperative DEXA screening, when appropriate, may offer objective data to inform templating and implant choices. Additionally, artificial intelligence-based planning tools that incorporate patient-specific clinical and radiological data could pave the way for more personalized and precise preoperative planning in the future.
Future studies incorporating quantitative bone quality assessment and longitudinal follow-up are warranted. Investigation into the impact of osteoporosis treatment on templating accuracy and postoperative outcomes could further refine preoperative planning protocols. Surgeons should consider systemic comorbidities when planning THA using 2D templating. Where feasible, adjunctive assessments of bone quality and potential use of 3D imaging may improve planning accuracy for these high-risk groups; 3D templating, however, comes at the expense of greater radiation exposure and cost [48], and therefore requires strict risk–benefit analysis for justification [49]. Additionally, surgical teams should prepare for possible intraoperative upsizing in patients with compromised bone quality to ensure appropriate implant availability and reduce intraoperative delays.
5. Conclusions
The results of our study showed that 2D digital templating is a reliable technique for preoperative planning in primary cementless THA. Osteoporosis significantly influences templating accuracy, often resulting in component oversizing. Orthopedic surgeons should consider these results preoperatively to improve planning and optimize surgery.
Author Contributions
Conceptualization, M.M. and P.M.; methodology: M.M.; software, P.M.; validation, G.G. and O.G.; formal analysis, E.C.; investigation, E.C. and P.M.; resources, F.F.; data curation, E.C.; writing—original draft preparation, C.E and L.M.; writing—review and editing, E.C., L.M. and M.M.; visualization, F.F.; supervision, O.G.; project administration, M.M. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board approval of Mater Domini Ethics Committee, ID number 14/2015.
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
Data are contained within the article.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Ding, X.; Zhang, B.; Li, W.; Huo, J.; Liu, S.; Wu, T.; Han, Y. Value of Preoperative Three-Dimensional Planning Software (AI-HIP) in Primary Total Hip Arthroplasty: A Retrospective Study. J. Int. Med. Res. 2021, 49, 03000605211058874. [Google Scholar] [CrossRef] [Scilit]
- Mercurio, M.; Gasparini, G.; Carbone, E.A.; Galasso, O.; Segura-Garcia, C. Personality Traits Predict Residual Pain after Total Hip and Knee Arthroplasty. Int. Orthop. 2020, 44, 1263–1270. [Google Scholar] [CrossRef] [Scilit]
- Luger, M.; Feldler, S.; Schauer, B.; Hochgatterer, R.; Gotterbarm, T.; Klasan, A. Digital Templating Cementless Short Stem Total Hip Arthroplasty: Is There a Difference in Planning Adherence between the Direct Anterior Approach and Minimally Invasive Anterolateral Approach? Arch. Orthop. Trauma Surg. 2023, 143, 1619–1626. [Google Scholar] [CrossRef] [Scilit]
- Mainard, D.; Barbier, O.; Knafo, Y.; Belleville, R.; Mainard-Simard, L.; Gross, J.-B. Accuracy and Reproducibility of Preoperative Three-Dimensional Planning for Total Hip Arthroplasty Using Biplanar Low-Dose Radiographs: A Pilot Study. Orthop. Traumatol. Surg. Res. 2017, 103, 531–536. [Google Scholar] [CrossRef] [Scilit]
- Brenneis, M.; Braun, S.; van Drongelen, S.; Fey, B.; Tarhan, T.; Stief, F.; Meurer, A. Accuracy of Preoperative Templating in Total Hip Arthroplasty with Special Focus on Stem Morphology: A Randomized Comparison Between Common Digital and Three-Dimensional Planning Using Biplanar Radiographs. J. Arthroplast. 2021, 36, 1149–1155. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- White, S.P.; Bainbridge, J.; Smith, E.J. Assessment of Magnification of Digital Pelvic Radiographs in Total Hip Arthroplasty Using Templating software. Ann. R. Coll. Surg. Engl. 2008, 90, 592–596. [Google Scholar] [CrossRef] [Scilit]
- Parisi, F.R.; Zampogna, B.; Zampoli, A.; Ferrini, A.; Albimonti, G.; Del Monaco, A.; Za, P.; Papalia, G.F.; Papalia, R. Planning Accuracy and Stem Offset Assessment in Digital Two-Dimensional Versus Three-Dimensional Planning in Cementless Hip Arthroplasty: A Systematic Review and Meta-Analysis. J. Clin. Med. 2024, 13, 6566. [Google Scholar] [CrossRef] [Scilit]
- Smith, J.B.V.; Bishi, H.; Wang, C.; Asopa, V.; Field, R.E.; Sochart, D.H. The Accuracy and Reliability of Preoperative Digital 2D Templating in Prosthesis Size Prediction in Uncemented versus Cemented Total Hip Arthroplasty: A Systematic Review and Meta-Analysis. EFORT Open Rev. 2021, 6, 1020–1039. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bishi, H.; Smith, J.B.V.; Asopa, V.; Field, R.E.; Wang, C.; Sochart, D.H. Comparison of the Accuracy of 2D and 3D Templating Methods for Planning Primary Total Hip Replacement: A Systematic Review and Meta-Analysis. EFORT Open Rev. 2022, 7, 70. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Reinbacher, P.; Smolle, M.A.; Friesenbichler, J.; Draschl, A.; Leithner, A.; Maurer-Ertl, W. Pre-Operative Templating in THA Using a Short Stem System: Precision and Accuracy of 2D versus 3D Planning Method. J. Orthop. Traumatol. 2022, 23, 16. [Google Scholar] [CrossRef] [Scilit]
- Dammerer, D.; Keiler, A.; Herrnegger, S.; Putzer, D.; Strasser, S.; Liebensteiner, M. Accuracy of Digital Templating of Uncemented Total Hip Arthroplasty at a Certified Arthroplasty Center: A Retrospective Comparative Study. Arch. Orthop. Trauma Surg. 2022, 142, 2471–2480. [Google Scholar] [CrossRef] [Scilit]
- Bertz, A.; Indrekvam, K.; Ahmed, M.; Englund, E.; Sayed-Noor, A.S. Validity and Reliability of Preoperative Templating in Total Hip Arthroplasty Using a Digital Templating System. Skelet. Radiol. 2012, 41, 1245–1249. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Efe, T.; El Zayat, B.F.; Heyse, T.J.; Timmesfeld, N.; Fuchs-Winkelmann, S.; Schmitt, J. Precision of Preoperative Digital Templating in Total Hip Arthroplasty. Acta Orthop. Belg. 2011, 77, 616–621. [Google Scholar]
- Mirghaderi, S.P.; Sharifpour, S.; Moharrami, A.; Ahmadi, N.; Makuku, R.; Salimi, M.; Mortazavi, S.M.J. Determining the Accuracy of Preoperative Total Hip Replacement 2D Templating Using the mediCAD® Software. J. Orthop. Surg. Res. 2022, 17, 222. [Google Scholar] [CrossRef] [Scilit]
- Schiffner, E.; Latz, D.; Jungbluth, P.; Grassmann, J.P.; Tanner, S.; Karbowski, A.; Windolf, J.; Schneppendahl, J. Is Computerised 3D Templating More Accurate than 2D Templating to Predict Size of Components in Primary Total Hip Arthroplasty? Hip Int. 2019, 29, 270–275. [Google Scholar] [CrossRef] [Scilit]
- Holzer, L.A.; Scholler, G.; Wagner, S.; Friesenbichler, J.; Maurer-Ertl, W.; Leithner, A. The Accuracy of Digital Templating in Uncemented Total Hip Arthroplasty. Archthes Orthop. Trauma Surg. 2019, 139, 263–268. [Google Scholar] [CrossRef] [Scilit]
- Le, N.T.T.; Robinson, J.; Lewis, S.J. Obese Patients and Radiography Literature: What Do We Know about a Big Issue? J. Med. Radiat. Sci. 2015, 62, 132. [Google Scholar] [CrossRef] [Scilit]
- Schapira, B.; Madanipour, S.; Iranpour, F.; Subramanian, P. Accuracy of Total Hip Arthroplasty Templating Using Set Calibration Magnifications. Cureus 2023, 15, e34883. [Google Scholar] [CrossRef] [Scilit]
- Sershon, R.A.; Diaz, A.; Bohl, D.D.; Levine, B.R. Effect of Body Mass Index on Digital Templating for Total Hip Arthroplasty. J. Arthroplast. 2017, 32, 1024–1026. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sözen, T.; Özışık, L.; Başaran, N.Ç. An Overview and Management of Osteoporosis. Eur. J. Rheumatol. 2016, 4, 46. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karia, M.; Abouharb, A.; Sabharwal, S.; Mavroveli, S.; Cobb, J. Impact of Bone Quality on Surgical Decision-Making in Total Hip Arthroplasty: A Qualitative Analysis in the UK. BMJ Open 2025, 15, e088081. [Google Scholar] [CrossRef] [Scilit]
- Pétursson, Þ.; Edmunds, K.J.; Gíslason, M.K.; Magnússon, B.; Magnúsdóttir, G.; Halldórsson, G.; Jónsson, H., Jr.; Gargiulo, P. Bone Mineral Density and Fracture Risk Assessment to Optimize Prosthesis Selection in Total Hip Replacement. Comput. Math. Methods Med. 2015, 2015, 162481. [Google Scholar] [CrossRef] [Scilit]
- Izzo, C.; Secondulfo, C.; Bilancio, G.; Visco, V.; Virtuoso, N.; Migliarino, S.; Ciccarelli, M.; Di Pietro, P.; La Mura, L.; Damato, A.; et al. Chronic Kidney Disease with Mineral Bone Disorder and Vascular Calcification: An Overview. Life 2024, 14, 418. [Google Scholar] [CrossRef] [Scilit]
- Ketteler, M.; Evenepoel, P.; Holden, R.M.; Isakova, T.; Jørgensen, H.S.; Komaba, H.; Nickolas, T.L.; Sinha, S.; Vervloet, M.G.; Cheung, M.; et al. Chronic Kidney Disease-Mineral and Bone Disorder: Conclusions from a Kidney Disease: Improving Global Outcomes (KDIGO) Controversies Conference. Kidney Int. 2025, 107, 405–423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nilsson, A.G.; Sundh, D.; Johansson, L.; Nilsson, M.; Mellström, D.; Rudäng, R.; Zoulakis, M.; Wallander, M.; Darelid, A.; Lorentzon, M. Type 2 Diabetes Mellitus Is Associated with Better Bone Microarchitecture but Lower Bone Material Strength and Poorer Physical Function in Elderly Women: A Population-Based Study. J. Bone Miner. Res. 2017, 32, 1062–1071. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Picke, A.-K.; Campbell, G.; Napoli, N.; Hofbauer, L.C.; Rauner, M. Update on the Impact of Type 2 Diabetes Mellitus on Bone Metabolism and Material Properties. Endocr. Connect. 2019, 8, R55. [Google Scholar] [CrossRef] [Scilit]
- Yacine, A.; Zain Ali, M.; Alharbi, A.B.; Qubayl Alanaz, H.; Saud Alrahili, A.; Alkhdairi, A.A. Chronic Inflammation: A Multidisciplinary Analysis of Shared Pathways in Autoimmune, Infectious, and Degenerative Diseases. Cureus 2025, 17, e82579. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Uccella, S.; Dottermusch, M.; Erickson, L.; Warmbier, J.; Montone, K.; Saeger, W. Inflammatory and Infectious Disorders in Endocrine Pathology. Endocr. Pathol. 2023, 34, 406–436. [Google Scholar] [CrossRef] [Scilit]
- Kristoffersson, E.; Otten, V.; Crnalic, S. The accuracy of digital templating in cementless total hip arthroplasty in dysplastic hips. BMC Musculoskelet. Disord. 2021, 22, 942. [Google Scholar] [CrossRef] [Scilit]
- Castioni, D.; Galasso, O.; Iannò, B.; Mercurio, M.; Gasparini, G. Posterior versus Lateral Surgical Approach: Functionality and Quality of Life after Total Hip Arthroplasty in a Matched Cohort Study. BMC Musculoskelet. Disord. 2021, 22, 932. [Google Scholar] [CrossRef] [Scilit]
- Falck-Ytter, Y.; Francis, C.W.; Johanson, N.A.; Curley, C.; Dahl, O.E.; Schulman, S.; Ortel, T.L.; Pauker, S.G.; Colwell, C.W. Prevention of VTE in Orthopedic Surgery Patients: Antithrombotic Therapy and Prevention of Thrombosis, 9th Ed: American College of Chest Physicians Evidence-Based Clinical Practice Guidelines. Chest 2012, 141, e278S–e325S. [Google Scholar] [CrossRef] [Scilit]
- Fillingham, Y.A.; Della Valle, C.J.; Suleiman, L.I.; Springer, B.D.; Gehrke, T.; Bini, S.A.; Segreti, J.; Chen, A.F.; Goswami, K.; Tan, T.L.; et al. Definition of Successful Infection Management and Guidelines for Reporting of Outcomes After Surgical Treatment of Periprosthetic Joint Infection: From the Workgroup of the Musculoskeletal Infection Society (MSIS). J. Bone Jt. Surg. Am. 2019, 101, e69. [Google Scholar] [CrossRef] [Scilit]
- Grappiolo, G.; Bruno, C.F.; Loppini, M.; Mercurio, M.; Castioni, D.; Gasparini, G.; Galasso, O. Conversion of Fused Hip to Total Hip Arthroplasty: Long-Term Clinical and Radiological Outcomes. J. Arthroplast. 2021, 36, 1060–1066. [Google Scholar] [CrossRef] [Scilit]
- Cerciello, S.; Mercurio, M.; Corona, K.; Proietti, L.; Di Vico, G.; Giordano, M.C.; Morris, B.J. Posterior Cruciate Buckling Angle Variations Are Associated with Different Patterns of Medial Meniscus Tears in Anterior-Cruciate-Deficient Knees: Results of a Prospective Comparative Magnetic Imaging Resonance Study. Healthcare 2024, 12, 1553. [Google Scholar] [CrossRef] [Scilit]
- Landis, J.R.; Koch, G.G. The Measurement of Observer Agreement for Categorical Data. Biometrics 1977, 33, 159–174. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shaarani, S.R.; McHugh, G.; Collins, D.A. Accuracy of Digital Preoperative Templating in 100 Consecutive Uncemented Total Hip Arthroplasties: A Single Surgeon Series. J. Arthroplast. 2013, 28, 331–337. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Almeida, D.F.; Ruben, R.B.; Folgado, J.; Fernandes, P.R.; Audenaert, E.; Verhegghe, B.; De Beule, M. Fully automatic segmentation of femurs with medullary canal definition in high and in low resolution CT scans. Med. Eng. Phys. 2016, 38, 1474–1480. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Daher, M.; Mekhael, E.; El-Othmani, M.M. Total Hip Arthroplasty in Patients with Hip Osteoporosis: A Narrative Review. Hip Pelvis 2024, 36, 260–272. [Google Scholar] [CrossRef] [Scilit]
- Dash, A.S.; Billings, E.; Vlastaris, K.; Kim, H.J.; Cunningham, M.E.; Raphael, J.; Lovecchio, F.; Carrino, J.A.; Lebl, D.; McMahon, D.; et al. Pre-Operative Bone Quality Deficits and Risk of Complications Following Spine Fusion Surgery among Postmenopausal Women. Osteoporos. Int. 2024, 35, 551–560. [Google Scholar] [CrossRef] [Scilit]
- Mercurio, M.; Familiari, F.; de Filippis, R.; Varano, C.; Napoleone, F.; Galasso, O.; Gasparini, G. Improvement in Health Status and Quality of Life in Patients with Osteoporosis Treated with Denosumab: Results at a Mean Follow-up of Six Years. Eur. Rev. Med. Pharmacol. Sci. 2022, 26, 16–23. [Google Scholar] [CrossRef] [Scilit]
- Fiedler, B.; Patel, V.; Lygrisse, K.A.; Kelly, M.E.; Turcotte, J.J.; MacDonald, J.; Schwarzkopf, R. The Effect of Reduced Bone Mineral Density on Elective Total Hip Arthroplasty Outcomes. Arch. Orthop. Trauma. Surg. 2023, 143, 5993–5999. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sariali, E.; Mauprivez, R.; Khiami, F.; Pascal-Mousselard, H.; Catonné, Y. Accuracy of the preoperative planning for cementless total hip arthroplasty. A randomised comparison between three-dimensional computerised planning and conventional templating. Orthop. Traumatol. Surg. Res. 2012, 98, 151–158. [Google Scholar] [CrossRef] [Scilit]
- Pansard, E.; Vigan, M.; Bauer, T. Do the sizes of total hip arthroplasty implants match between 3D planning software and 2D templating? Orthop. Traumatol. Surg. Res. 2024, 110, 103744. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meyer, M.; Leiß, F.; Götz, J.S.; Holzapfel, D.E.; Grifka, J.; Weber, M. Bone Mineral Density Is Associated with Adverse Events but Not Patient-Reported Outcomes in Total Hip and Knee Arthroplasty. J. Arthroplast. 2024, 39, 320–325. [Google Scholar] [CrossRef] [Scilit]
- Layson, J.T.; Hameed, D.; Dubin, J.A.; Moore, M.C.; Mont, M.; Scuderi, G.R. Patients with Osteoporosis Are at Higher Risk for Periprosthetic Femoral Fractures and Aseptic Loosening Following Total Hip Arthroplasty. Orthop. Clin. North. Am. 2024, 55, 311–321. [Google Scholar] [CrossRef] [Scilit]
- Harris, A.B.; Lantieri, M.A.; Agarwal, A.R.; Golladay, G.J.; Thakkar, S.C. Osteoporosis and Total Knee Arthroplasty: Higher 5-Year Implant-Related Complications. J. Arthroplast. 2024, 39, 948–953.e1. [Google Scholar] [CrossRef] [Scilit]
- Mercurio, M.; de Filippis, R.; Spina, G.; De Fazio, P.; Segura-Garcia, C.; Galasso, O.; Gasparini, G. The Use of Antidepressants Is Linked to Bone Loss: A Systematic Review and Metanalysis. Orthop. Rev. 2022, 14, 38564. [Google Scholar] [CrossRef] [Scilit]
- Osmani, F.A.; Thakkar, S.; Ramme, A.; Elbuluk, A.; Wojack, P.; Vigdorchik, J.M. Variance in Predicted Cup Size by 2-dimensional vs 3-Dimensional Computerized Tomography-Based Templating in Primary Total Hip Arthroplasty. Arthroplast. Today 2017, 3, 289–293. [Google Scholar] [CrossRef] [Scilit]
- Huppertz, A.; Radmer, S.; Asbach, P.; Juran, R.; Schwenke, C.; Diederichs, G.; Hamm, B.; Sparmann, M. Computed Tomography for Preoperative Planning in Minimal-Invasive Total Hip Arthroplasty: Radiation Exposure and Cost Analysis. Eur. J. Radiol. 2011, 78, 406–413. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).