1. Introduction
Inclisiran is a small interfering RNA that inhibits the hepatic synthesis of proprotein convertase subtilisin/kexin type 9 (PCSK9), thereby increasing low-density lipoprotein receptor recycling and lowering circulating low-density lipoprotein cholesterol (LDL-C). In the pivotal ORION-10 and ORION-11 trials, inclisiran treatment administered on days 1 and 90 and every 6 months thereafter produced approximately 50% placebo-corrected LDL-C reductions over 18 months, and subsequent pooled and extension analyses supported sustained lipid lowering with an infrequent maintenance dosing strategy [
1,
2,
3]. Although the LDL-C-lowering efficacy of inclisiran is well established, longitudinal changes in coronary plaque burden and composition after its initiation remain incompletely characterized, particularly in routine clinical settings.
The biological rationale for evaluating the coronary plaque response after PCSK9-targeted therapy is supported by prior imaging studies on monoclonal antibody-type PCSK9 inhibition. In the GLAGOV randomized trial, evolocumab added to statin therapy achieved substantially lower LDL-C levels and greater intravascular ultrasound-defined coronary atheroma regression than the placebo [
4]. More recent multimodal intracoronary imaging studies, including HUYGENS and PACMAN-AMI, further suggested that intensive PCSK9 inhibition in addition to statin therapy can favorably modify the plaque phenotype, including fibrous-cap thickening, lipid-arc reduction, macrophage signal reduction, and plaque regression [
5,
6]. These studies provide an important mechanistic context, but their findings cannot be directly extrapolated to inclisiran or noninvasive CCTA-based plaque characterization.
Serial coronary computed tomography angiography (CCTA) has emerged as a practical and noninvasive approach for assessing the progression of coronary atherosclerosis and treatment-associated plaque remodeling over time [
7,
8]. In serial CCTA cohorts, statin therapy has been associated not only with slower overall plaque progression but also with compositional transformation, including reduced low-attenuation or non-calcified plaque components and increased calcified or higher-density components [
9,
10]. Therefore, CCTA-based plaque composition provides a clinically interpretable framework for evaluating whether profound LDL-C lowering is accompanied by a shift toward a more stable plaque phenotype, even when the total plaque volume changes are modest.
Simultaneously, quantitative CCTA plaque assessment remains methodologically complex. Contemporary consensus documents emphasize the need for standardized acquisition, segmentation, reporting, and interpretation of plaque burden and composition, while also recognizing that attenuation-based thresholds and software-specific definitions may differ across platforms [
11,
12,
13]. Artificial intelligence (AI)-assisted CCTA tools may improve reproducibility, reduce operator dependence, and facilitate scalable longitudinal plaque monitoring. However, real-world evidence using fully automated, nonmanual correction workflows remains limited [
14,
15].
Accordingly, we aimed to evaluate longitudinal changes in coronary plaque composition after the initiation of inclisiran treatment using fully automated AI-assisted CCTA. We specifically assessed changes in the total plaque volume, total non-calcified plaque (NCP), low-density non-calcified plaque (LDNC), and calcified plaque volume; evaluated the relationship between LDL-C reduction and LDNC reduction; and performed hypothesis-generating subgroup analyses according to acute coronary syndrome (ACS) versus chronic coronary syndrome (CCS) presentation.
2. Materials and Methods
2.1. Study Design and Patient Population
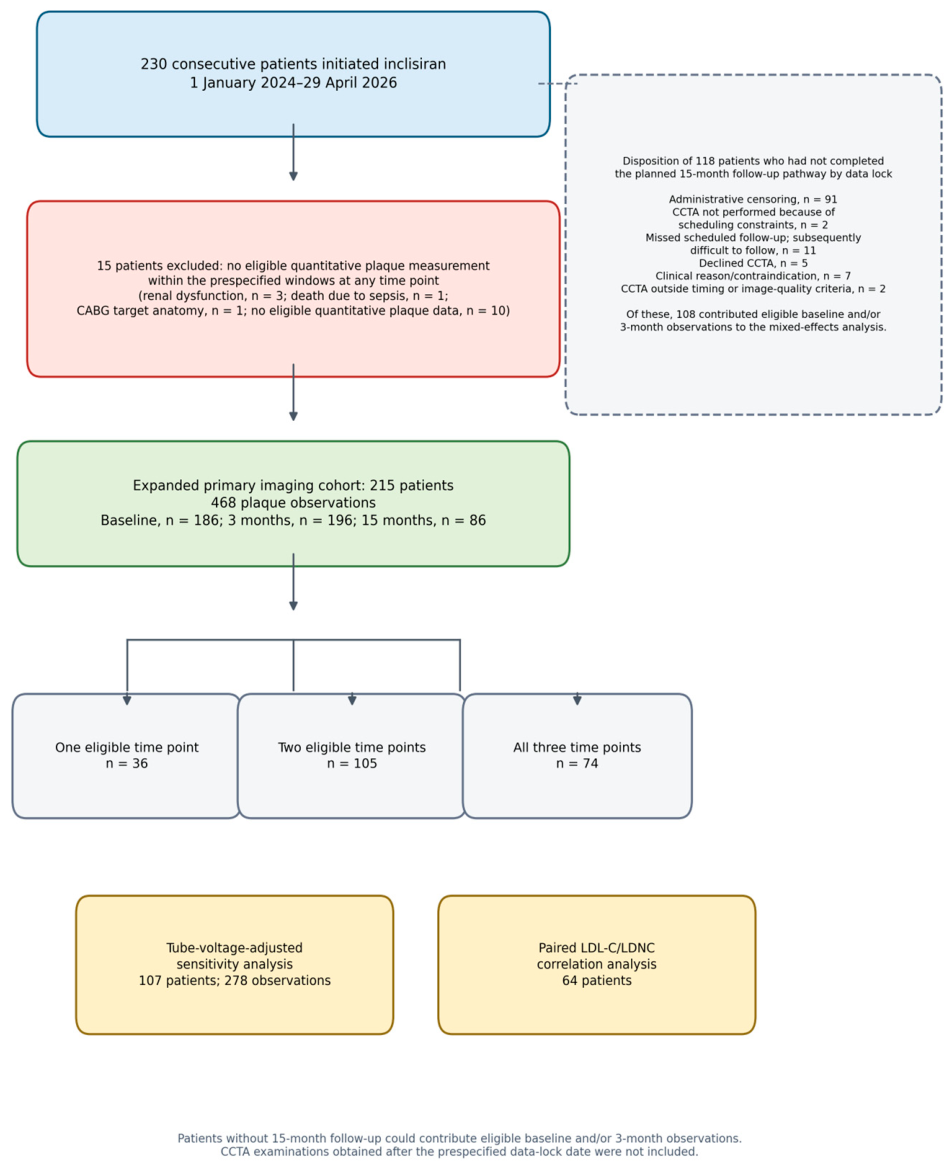
This single-center, retrospective, observational pilot study was conducted at Minamino Cardiovascular Hospital. Follow-up CCTA at approximately 3 and 15 months was prospectively scheduled as part of an institutional clinical-care protocol for assessing treatment response after inclisiran initiation and was not performed specifically for the present research. The present study retrospectively analyzed existing imaging and clinical data generated during routine care. Consecutive patients who initiated inclisiran between 1 January 2024 and 29 April 2026 were screened.
The final data lock date was 29 April 2026. Because the treatment-initiation window extended through the data lock date, patients who initiated treatment later in the window had not yet accrued 15 months of follow-up at data lock. Baseline CCTA was defined as an eligible routine care examination performed before or on the day of inclisiran initiation. No maximum look-back interval was imposed in the primary retrospective extraction; examinations performed more than 90 days before treatment were retained because they met the prespecified pretreatment baseline definition, and their influence was assessed in the sensitivity analysis. The 3- and 15-month examinations were identified using prespecified clinical windows of ±14 days. Examinations obtained after the data lock date were not included. The primary longitudinal analysis included every eligible quantitative plaque measurement available by the data lock date, irrespective of whether the patient completed 15 months of imaging.
2.2. CCTA Acquisition Protocol
The CCTA examinations were performed using an APEX Elite 256-row scanner (GE Healthcare, Chicago, IL, USA) with non-helical, prospectively electrocardiogram-triggered acquisition, automatic exposure control, and 0.625-mm slice thickness. The images were reconstructed using the HD Standard kernel and a strong level of iterative reconstruction. The cardiac phase with the least motion artifact was selected, and SnapShot Freeze 2.0 motion-correction processing was applied. Tube voltage was 120 or 140 kVp according to the patient and scanning conditions. Iodinated contrast medium (240 mg I/mL) was administered over a fixed 13-s injection period, followed by a 30-mL saline flush at the same injection rate. To reduce differences in intraluminal coronary attenuation between tube voltage protocols, the iodine delivery rate was adjusted to 20 mg I/kg/s at 120 kVp and 23 mg I/kg/s at 140 kVp. No post-processing normalization of plaque attenuation according to tube voltage was performed. Sublingual nitroglycerin was administered unless clinically contraindicated; beta-blockers were not administered routinely. CTDIvol and dose-length product (DLP) were retrospectively retrieved when available. The effective dose was estimated as DLP multiplied by 0.014 mSv/(mGy·cm) [
16].
2.3. AI-Assisted Plaque Quantification and Outcomes
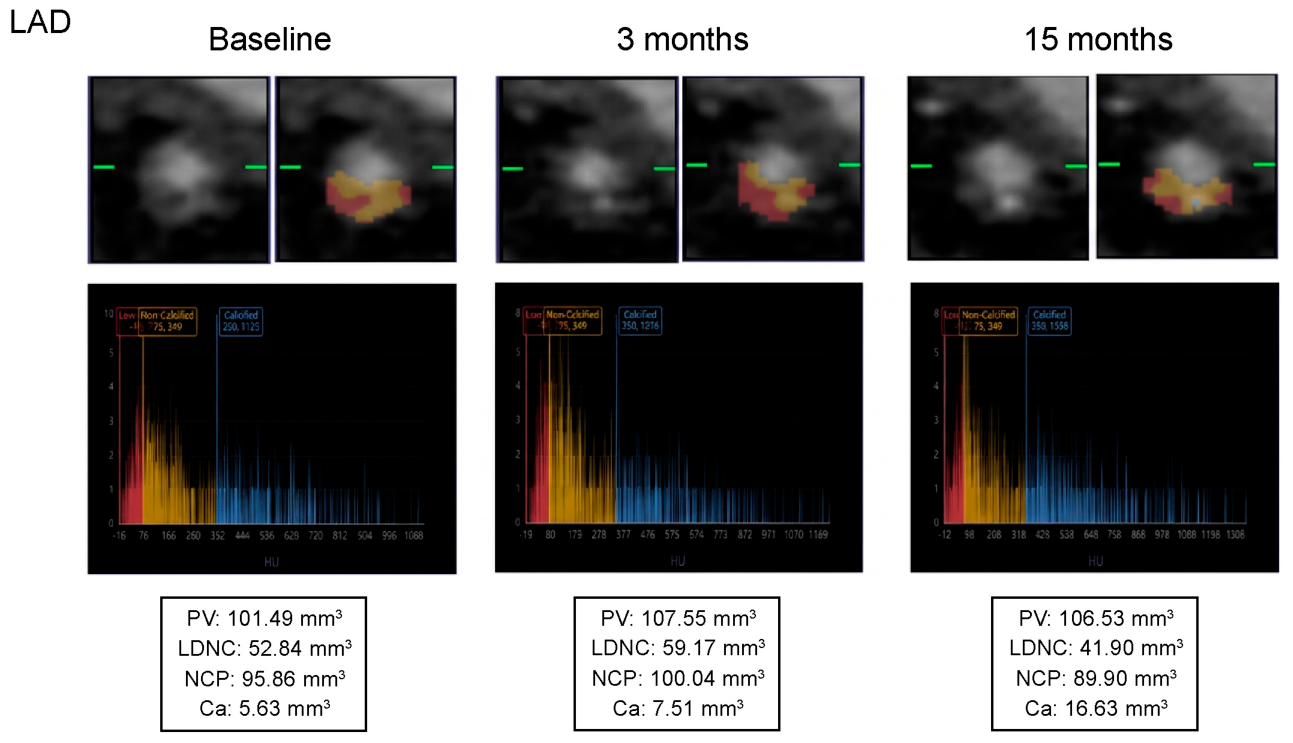
The coronary plaque analysis was performed using CoronaryDoc (version 2.0.0.001; Shukun Technology, Beijing, China). Quantification was fully automated without manual correction. The same software version was used for all examinations. All automated outputs underwent visual quality control review. No examination was excluded because of an unanalyzable output or complete segmentation failure. The analyst was not blinded to the examination time point or clinical information. According to the software manual, coronary arteries with a reference vessel diameter of ≥1.5 mm were intended for automated analysis; however, smaller distal vessels could also be recognized depending on attenuation and the anatomical course. No additional post-processing exclusion was applied solely on the basis of the vessel diameter. The same coronary arteries were evaluated at each available time point, while the analyzed range was automatically extracted independently by the software at each examination. Strict point-by-point anatomical coregistration of identical coronary segments was not performed. Previously implanted stents were automatically identified and excluded. Patients undergoing percutaneous coronary intervention during the follow-up remained eligible, but only the treated coronary segments, including newly stented segments, were excluded; untreated segments remained available for the longitudinal analysis. Plaque components were prespecified as total NCP (−30 to <350 HU), investigator-defined LDNC (−30 to <75 HU, a subset of NCP), and calcified plaque (≥350 HU). The 75-HU upper threshold was selected on the basis of histopathologic validation showing quantitative agreement between the CCTA-derived low-attenuation plaque area and histologic lipid-rich plaque area [
17]. These thresholds were applied uniformly to all patients and time points, and component volumes were directly quantified by the software. The primary outcomes were longitudinal changes in the LDL-C, total plaque, total NCP, LDNC, and calcified plaque volumes.
2.4. Statistical Analysis
Baseline characteristics are presented as mean ± standard deviation for continuous variables and as number (percentage) for categorical variables. Longitudinal model-derived values are presented as estimated marginal means with 95% confidence intervals (CIs).
Longitudinal changes were assessed using a linear mixed-effects model with time modeled categorically as a fixed effect and patient as a random intercept, yielding a compound-symmetry covariance structure. All the eligible observations available by the data lock date were included without imputation. Model-estimated means, 95% CIs, and overall time effects are reported. Three pairwise time contrasts were evaluated within each outcome with Bonferroni-adjusted p-values. To address multiplicity across the five overall outcome tests, Benjamini–Hochberg false discovery rate-adjustment was additionally considered. As an acquisition-parameter sensitivity analysis, the tube voltage (120 versus 140 kVp) was included as a time-varying fixed-effect covariate in the subset with linkable tube voltage data. Plaque volume residuals were right-skewed; therefore, complete-case and prespecified sensitivity analyses were used to assess robustness. Results were interpreted as exploratory rather than confirmatory.
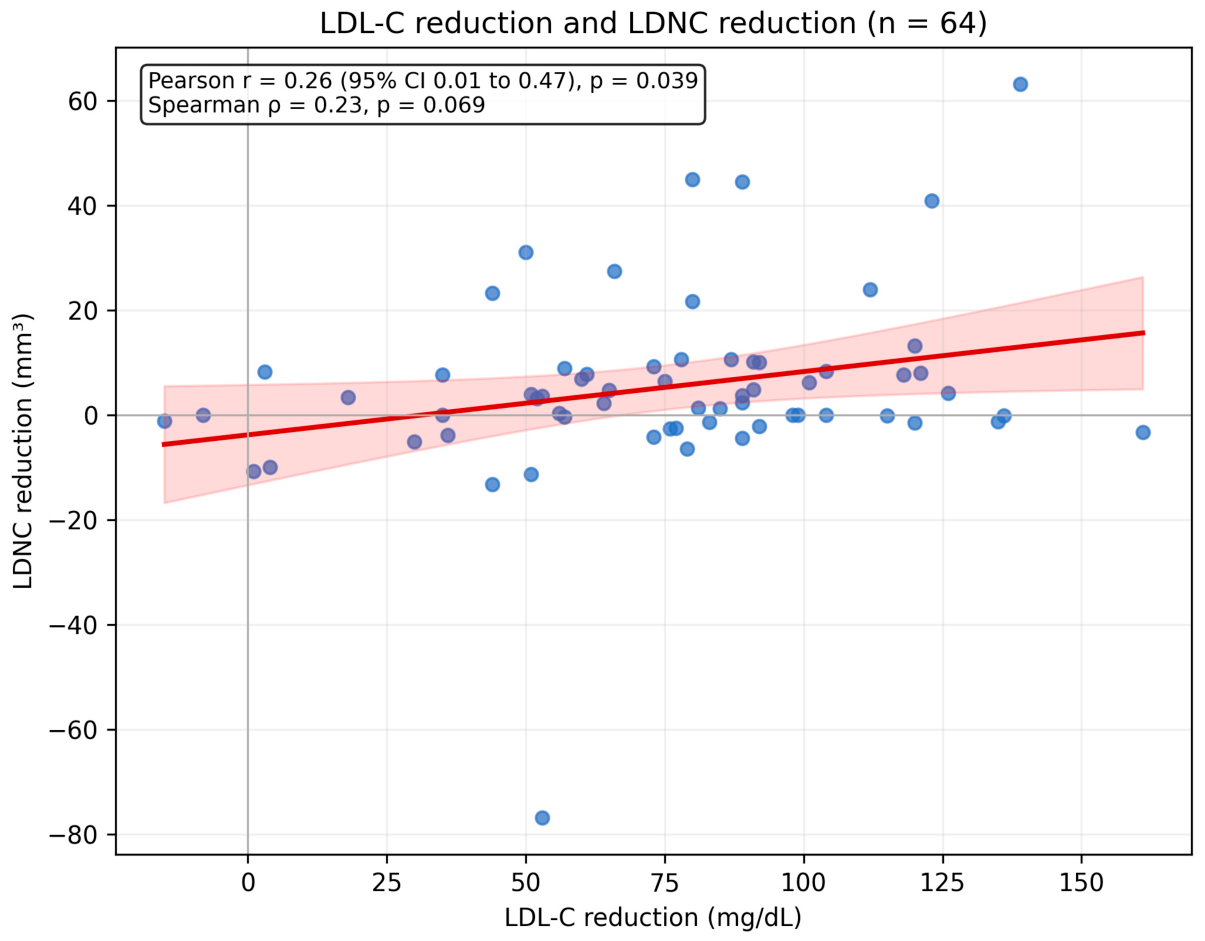
The paired baseline-to-15-month LDL-C/LDNC subset (n = 64) was analyzed using the Pearson and Spearman correlations. Pearson 95% CIs were calculated using the Fisher z transformation. The sensitivity analysis excluded observations with an absolute standardized value > 2 for either change score. The ACS-versus-CCS analyses included time-by-group interaction terms. All tests were two-sided; p < 0.05 was considered statistically significant, with adjusted p-values reported where applicable.
2.5. Use of Generative AI in Manuscript Preparation
Generative AI was used only to assist manuscript preparation and revision. ChatGPT, including the Codex workspace (OpenAI, San Francisco, CA, USA; web-based service accessed on 5 September 2026; the specific model version was not displayed), was used for statistical code development, internal consistency checking, language refinement, and document formatting. Manus AI (Manus;
https://manus.im; web-based service accessed on 5 September 2026; no version number was displayed) was used only at the final revision stage to check language and consistency and suggest editorial revisions. Neither tool was used to define the study design, generate or alter primary study data, or quantify CCTA outcomes; CCTA plaque quantification was performed separately with CoronaryDoc as described earlier. All AI-assisted code, analytical output, figures, and text were reviewed and verified by the authors. The study statistician independently reproduced the principal mixed-effects analyses, and the authors take full responsibility for the content of this publication.
2.6. Ethics Statements
This study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board of Minamino Cardiovascular Hospital (approval number: MJ-108; approval date: 27 April 2026). Written informed consent for participation and for the use of clinical data for research purposes was obtained from all participants.
4. Discussion
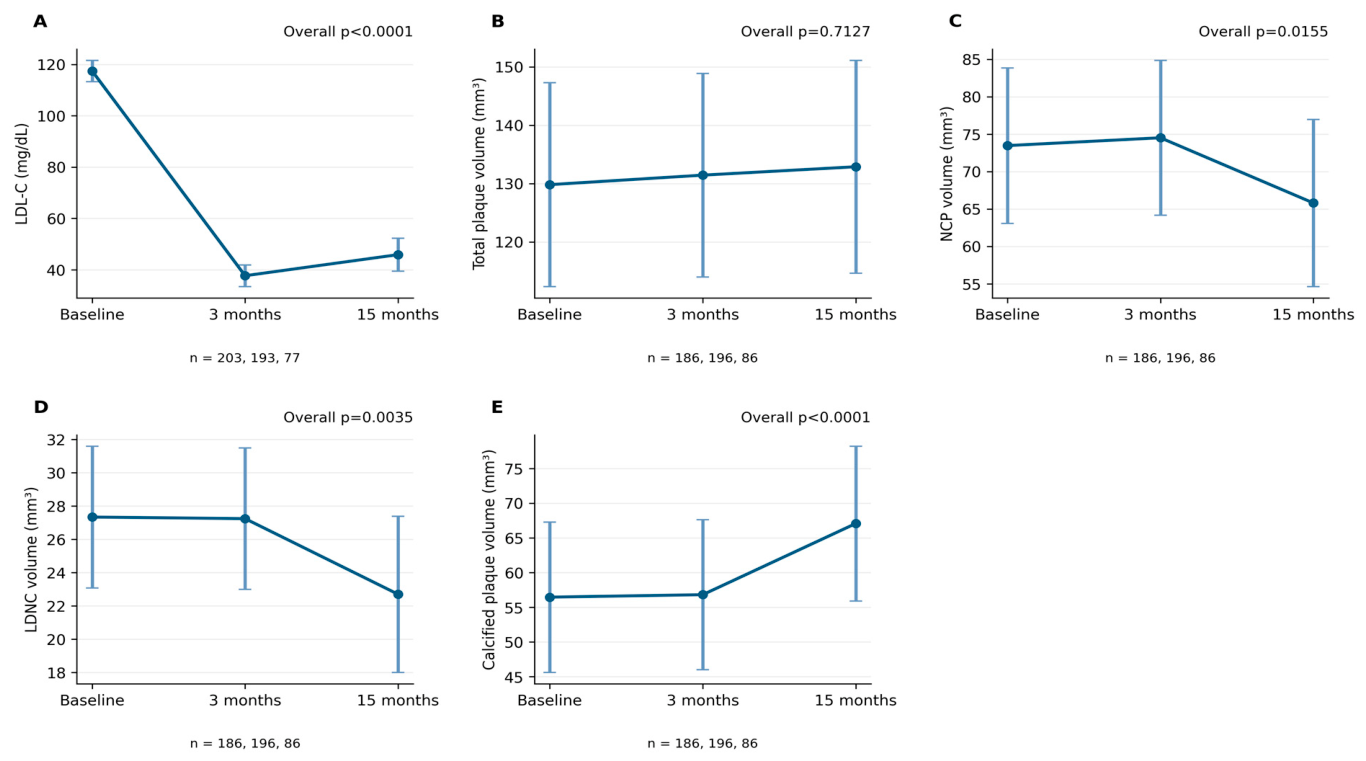
In this single-center, retrospective pilot study, automated CCTA showed temporal changes in attenuation-defined coronary plaque composition after inclisiran initiation. Incorporating every eligible quantitative plaque observation available by the prespecified data cutoff date increased the primary cohort from 107 to 215 patients. The LDL-C levels decreased markedly; no significant time effect was detected for the total plaque volume; LDNC and total NCP decreased; and calcified plaque increased. The principal detectable imaging signal over 15 months was, therefore, a measured compositional shift rather than global plaque regression. These findings do not establish biological plaque stabilization or an inclisiran effect.
This observation should be interpreted within the broader literature on intensive lipid lowering and plaque stabilization. Invasive imaging trials of monoclonal antibody-type PCSK9 inhibition, such as GLAGOV, HUYGENS, and PACMAN-AMI, have shown that very low LDL-C levels achieved with statin therapy can be accompanied by coronary atheroma regression and favorable plaque phenotype changes [
4,
5,
6]. Our study differs fundamentally from these trials because it evaluated inclisiran, used CCTA rather than intravascular ultrasound/optical coherence tomography, lacked a randomized control group, and was conducted in routine practice. Nevertheless, the direction of the observed changes is biologically plausible and concordant with the concept that intensive LDL-C reduction promotes plaque stabilization.
The combination of no significant time effect in total plaque volume with compositional change is consistent with results of the serial CCTA studies of intensive lipid lowering, in which reductions in lower-attenuation or non-calcified components may accompany increased calcification or plaque density [
9,
10]. LDNC was an investigator-defined quantitative component (−30 to <75 HU), not a direct histologic measurement. Importantly, LDNC reduction and calcified plaque increase remained significant after adjustment for tube voltage as a time-varying covariate in the 107-patient acquisition data subset. Nevertheless, attenuation measurements remain influenced by the tube voltage, luminal enhancement, reconstruction, partial-volume effects, and analysis platform. Therefore, the observed pattern should be interpreted as a software-specific attenuation-defined compositional change rather than as evidence of histologic transformation, biological stabilization, or causality.
Most patients received background statin therapy. Among the 74 complete cases, 65 had no recorded change in statin or ezetimibe therapy during the follow-up. In this no-change sensitivity cohort, the LDNC reduction and calcified plaque increase were preserved while the total plaque volume showed no significant time effect; the overall change in total NCP was not statistically significant. These findings reduce but do not eliminate concern that the principal compositional results were driven solely by changes in concomitant lipid-lowering therapy. Residual confounding by treatment intensity, adherence, and other risk factor management remains possible.
The fully automated AI workflow is another important methodological aspect of the current study. Manual correction can improve individual segmentation accuracy in selected cases; however, it also introduces operator dependence and limits scalability. By avoiding manual correction, the present analysis approximated how AI-assisted plaque quantification could function in routine clinical workflows and minimized investigator subjectivity. Simultaneously, this design choice may have allowed for residual segmentation, vessel-boundary, or component-classification errors. Therefore, the results should be regarded as workflow-level, software-specific observations rather than definitive histopathological characterization of plaque composition.
The Pearson association between the LDL-C and LDNC reductions was weak and was not corroborated by the findings of the Spearman analysis or outlier sensitivity analysis. Accordingly, this result should not be considered robust evidence of a dose–response relationship. Change-score correlations are also susceptible to baseline values, regression to the mean, and measurement error. Thus, the correlation analysis provides, at most, exploratory support for a possible relationship and does not materially strengthen causal interpretation.
The exploratory ACS-versus-CCS subgroup analyses did not identify statistically significant time-by-group interactions for any plaque metric; however, LDL-C trajectories differed between the groups. The study was not powered for interaction testing, and patients with ACS and those with CCS may differ in plaque biology, systemic inflammation, treatment intensity, and follow-up indications. Therefore, these subgroup findings should be viewed as descriptive reference data rather than as evidence of an equivalent treatment response.
This study has some limitations. Its retrospective single-center design and absence of an untreated or active-comparator group preclude causal attribution to inclisiran. Although the expanded mixed-effects analysis included every eligible quantitative plaque observation available by the prespecified data cutoff date, only 74 patients had complete three-time-point imaging, 36 contributed a single time point, and the missing data mechanism was not empirically verified. The 15-month observations necessarily came from patients who initiated treatment earlier, creating administrative censoring and potential selection bias. Although the key compositional findings persisted after excluding the remote baseline examinations, such scans may not precisely represent plaque status immediately before treatment initiation. The tube voltage data for the additionally incorporated baseline and 3-month examinations were not systematically available; therefore, tube voltage adjustment was restricted to 107 patients, and residual acquisition-related confounding in the expanded cohort cannot be excluded. In that subset, LDNC reduction and calcified plaque increase were maintained after adjustment, but the LDNC result was borderline. Luminal enhancement was not included in the model, and residual effects of contrast attenuation, reconstruction, partial-volume effects, and software-specific thresholds remain possible. Visual quality control was performed by an analyst who was not blinded, although no manual correction was made. Strict point-by-point coronary coregistration was not performed, and minor differences in analyzed boundaries remain possible. Concomitant treatment, ACS-related healing, intervention, adherence, and other risk factor management may also have contributed. Finally, this imaging biomarker study was not powered for clinical outcomes or subgroup interactions and did not assess repeatability. Despite these limitations, this study provides hypothesis-generating data on automated serial plaque assessment in routine clinical practice.




 ,