Case Report

Multimodal Imaging of a Post-Traumatic Cervical Arteriovenous Fistula with Concomitant Pseudoaneurysm After a Gunshot Wound Treated with a Covered Stent-Graft

by
Michał Chlabicz
1,
Łukasz Stypułkowski
2,*,
Mateusz Jadeszko
1,
Maciej Chlabicz
1 and
Jerzy Głowiński
1
1
Department of Vascular Surgery and Transplantation, Medical University of Białystok, ul. Jana Kilińskiego 1, 15-089 Bialystok, Poland
2
Faculty of Medicine with the Division of Dentistry and Division of Medical Education in English, Medical University of Białystok, ul. Jana Kilinskiego 1, 15-089 Bialystok, Poland
*
Author to whom correspondence should be addressed.
Diagnostics 2026, 16(15), 2411; https://doi.org/10.3390/diagnostics16152411
Submission received: 9 June 2026 / Revised: 18 July 2026 / Accepted: 27 July 2026 / Published: 31 July 2026
(This article belongs to the Special Issue Diagnosis and Management of Vascular Diseases)

Abstract

Background: Arteriovenous fistula is an abnormal connection between an artery and a vein. Post-traumatic fistulas are uncommon and usually occur after penetrating injuries, including gunshot wounds. Cervical arteriovenous fistulas are particularly rare and may coexist with a pseudoaneurysm, creating diagnostic and therapeutic challenges because of the proximity of major vascular, neurological, and aerodigestive structures. In hemodynamically stable patients, the limited external appearance of the wound may underestimate the extent of internal vascular injury; therefore, imaging is central to diagnosis and treatment planning. Case Presentation: We report the case of a 49-year-old man who presented to the emergency department with a gunshot wound to the left side of the neck. Computed tomography angiography (CTA) demonstrated a vascular injury adjacent to the left common carotid artery (LCCA), and further evaluation revealed an arteriovenous fistula (AVF) between the LCCA and the left internal jugular vein (LIJV), coexisting with a pseudoaneurysm of the LCCA. Doppler ultrasonography (DUS) identified an arterial wall defect and extrinsic compression of the LCCA by the hematoma. Selective digital subtraction angiography (DSA) confirmed an AVF between the LCCA and the LIJV, coexisting with an LCCA pseudoaneurysm. A covered stent-graft was implanted and completion angiography confirmed exclusion of both lesions with preserved patency of the LCCA. Discussion: This case demonstrates the complementary value of CTA, DUS and DSA in penetrating neck trauma. CTA provided rapid cross-sectional assessment of the injury trajectory and associated lesions, DUS added information on the arterial wall and local hemodynamic consequences, and DSA confirmed arteriovenous shunting while enabling immediate endovascular treatment. Conclusions: In hemodynamically stable patients with penetrating neck trauma, CTA should be considered when the wound trajectory approaches major vessels, even in the absence of active external bleeding. DUS and DSA may provide complementary information for lesion characterization and procedural planning. Covered stent-graft implantation may be a feasible reconstructive option in carefully selected patients.

1. Introduction

Arteriovenous fistula (AVF) is a pathological connection between an artery and a vein that allows blood to pass directly from the high-pressure arterial system into the low-pressure venous system [1,2,3,4]. Traumatic AVFs are uncommon and usually result from simultaneous or adjacent injury to an artery and a vein, most often after penetrating trauma such as gunshot or stab wounds [2,3,4,5,6]. The resulting communication may remain patent and mature into a persistent fistula. Depending on its size and location, an AVF may be clinically silent or may cause bruit, thrill, swelling, venous dilatation, progressive hematoma, distal ischemia, embolic complications or systemic hemodynamic effects [1,2,3,7].
Pseudoaneurysm is another important vascular consequence of trauma. In penetrating trauma, pseudoaneurysm and AVF may coexist when the arterial wall defect communicates both with a perivascular cavity and an adjacent venous structure. This combination is clinically relevant because it increases the risk of bleeding, embolic complications, local compression, delayed rupture, and venous hypertension [8,9,10].
The diagnosis of vascular injury after penetrating neck trauma is challenging because the neck contains the carotid and vertebral arteries, jugular veins, cranial nerves, airway, esophagus and cervical spine within a compact anatomical region. The selective no-zone approach is supported by systematic review [11,12] and is consistent with recent formal AAST-WSES guidelines on cervical vascular injuries, which recommend CTA in penetrating neck trauma without hard signs and advise against management based solely on the anatomical neck zone [13]. Patients with hard signs such as uncontrolled hemorrhage, expanding or pulsatile hematoma, refractory shock, airway compromise, bruit or thrill, or focal neurological deficit require immediate operative or endovascular management, whereas hemodynamically stable patients without hard signs are generally suitable for selective imaging-based evaluation, with CTA as the principal screening modality [11,12,14,15,16,17]. Doppler ultrasonography (DUS) may provide useful real-time information on vessel-wall integrity and flow, while digital subtraction angiography (DSA) remains important when CTA suggests a complex lesion and endovascular treatment is contemplated [8,9,10,11,12,14,15,18,19]. The main advantages and limitations of available imaging techniques are summarized in Table 1.
The treatment of traumatic AVFs and pseudoaneurysms should be individualized. Open repair remains essential in hemodynamically unstable patients, in the presence of contaminated or infected wounds, for lesions unsuitable for endovascular reconstruction or after failed endovascular treatment. In selected stable patients, covered stent-graft implantation may exclude the arterial defect and fistulous communication while preserving flow through the parent artery [5,9,10,18,19,20,21,22,23]. We present a rare post-traumatic cervical AVF between the left common carotid artery (LCCA) and left internal jugular vein (LIJV), coexisting with an LCCA pseudoaneurysm after a gunshot wound. The case illustrates the complementary roles of CTA, DUS, and DSA in detecting and characterizing a complex combined cervical vascular lesion and demonstrates how multimodal imaging can support the selection and planning of endovascular treatment with a covered stent-graft.

2. Case Presentation

2.1. Clinical Presentation

We present the case of a 49-year-old man with diabetes mellitus, coronary artery disease, and a history of myocardial infarction who presented to the emergency department after sustaining a penetrating, through-and-through gunshot injury to the left cervical region. On admission, the patient was in good general condition, with normal blood pressure and heart rate. Physical examination revealed edema and induration of the left side of the neck, as well as an entry wound measuring 1–2 mm in diameter, located 4–5 mm above the sternoclavicular joint. The exit wound also measured 1–2 mm in diameter and was located approximately 2 cm superior to the entry wound. There was no evidence of active bleeding.
Admission laboratory tests showed a hemoglobin concentration of 13.8 g/dL, red blood cell count of 4.51 × 10⁶/µL, white blood cell count of 8.59 × 10³/µL, and platelet count of 167 × 103/µL. Coagulation parameters were within the reference range.

2.2. Diagnostic Work-Up

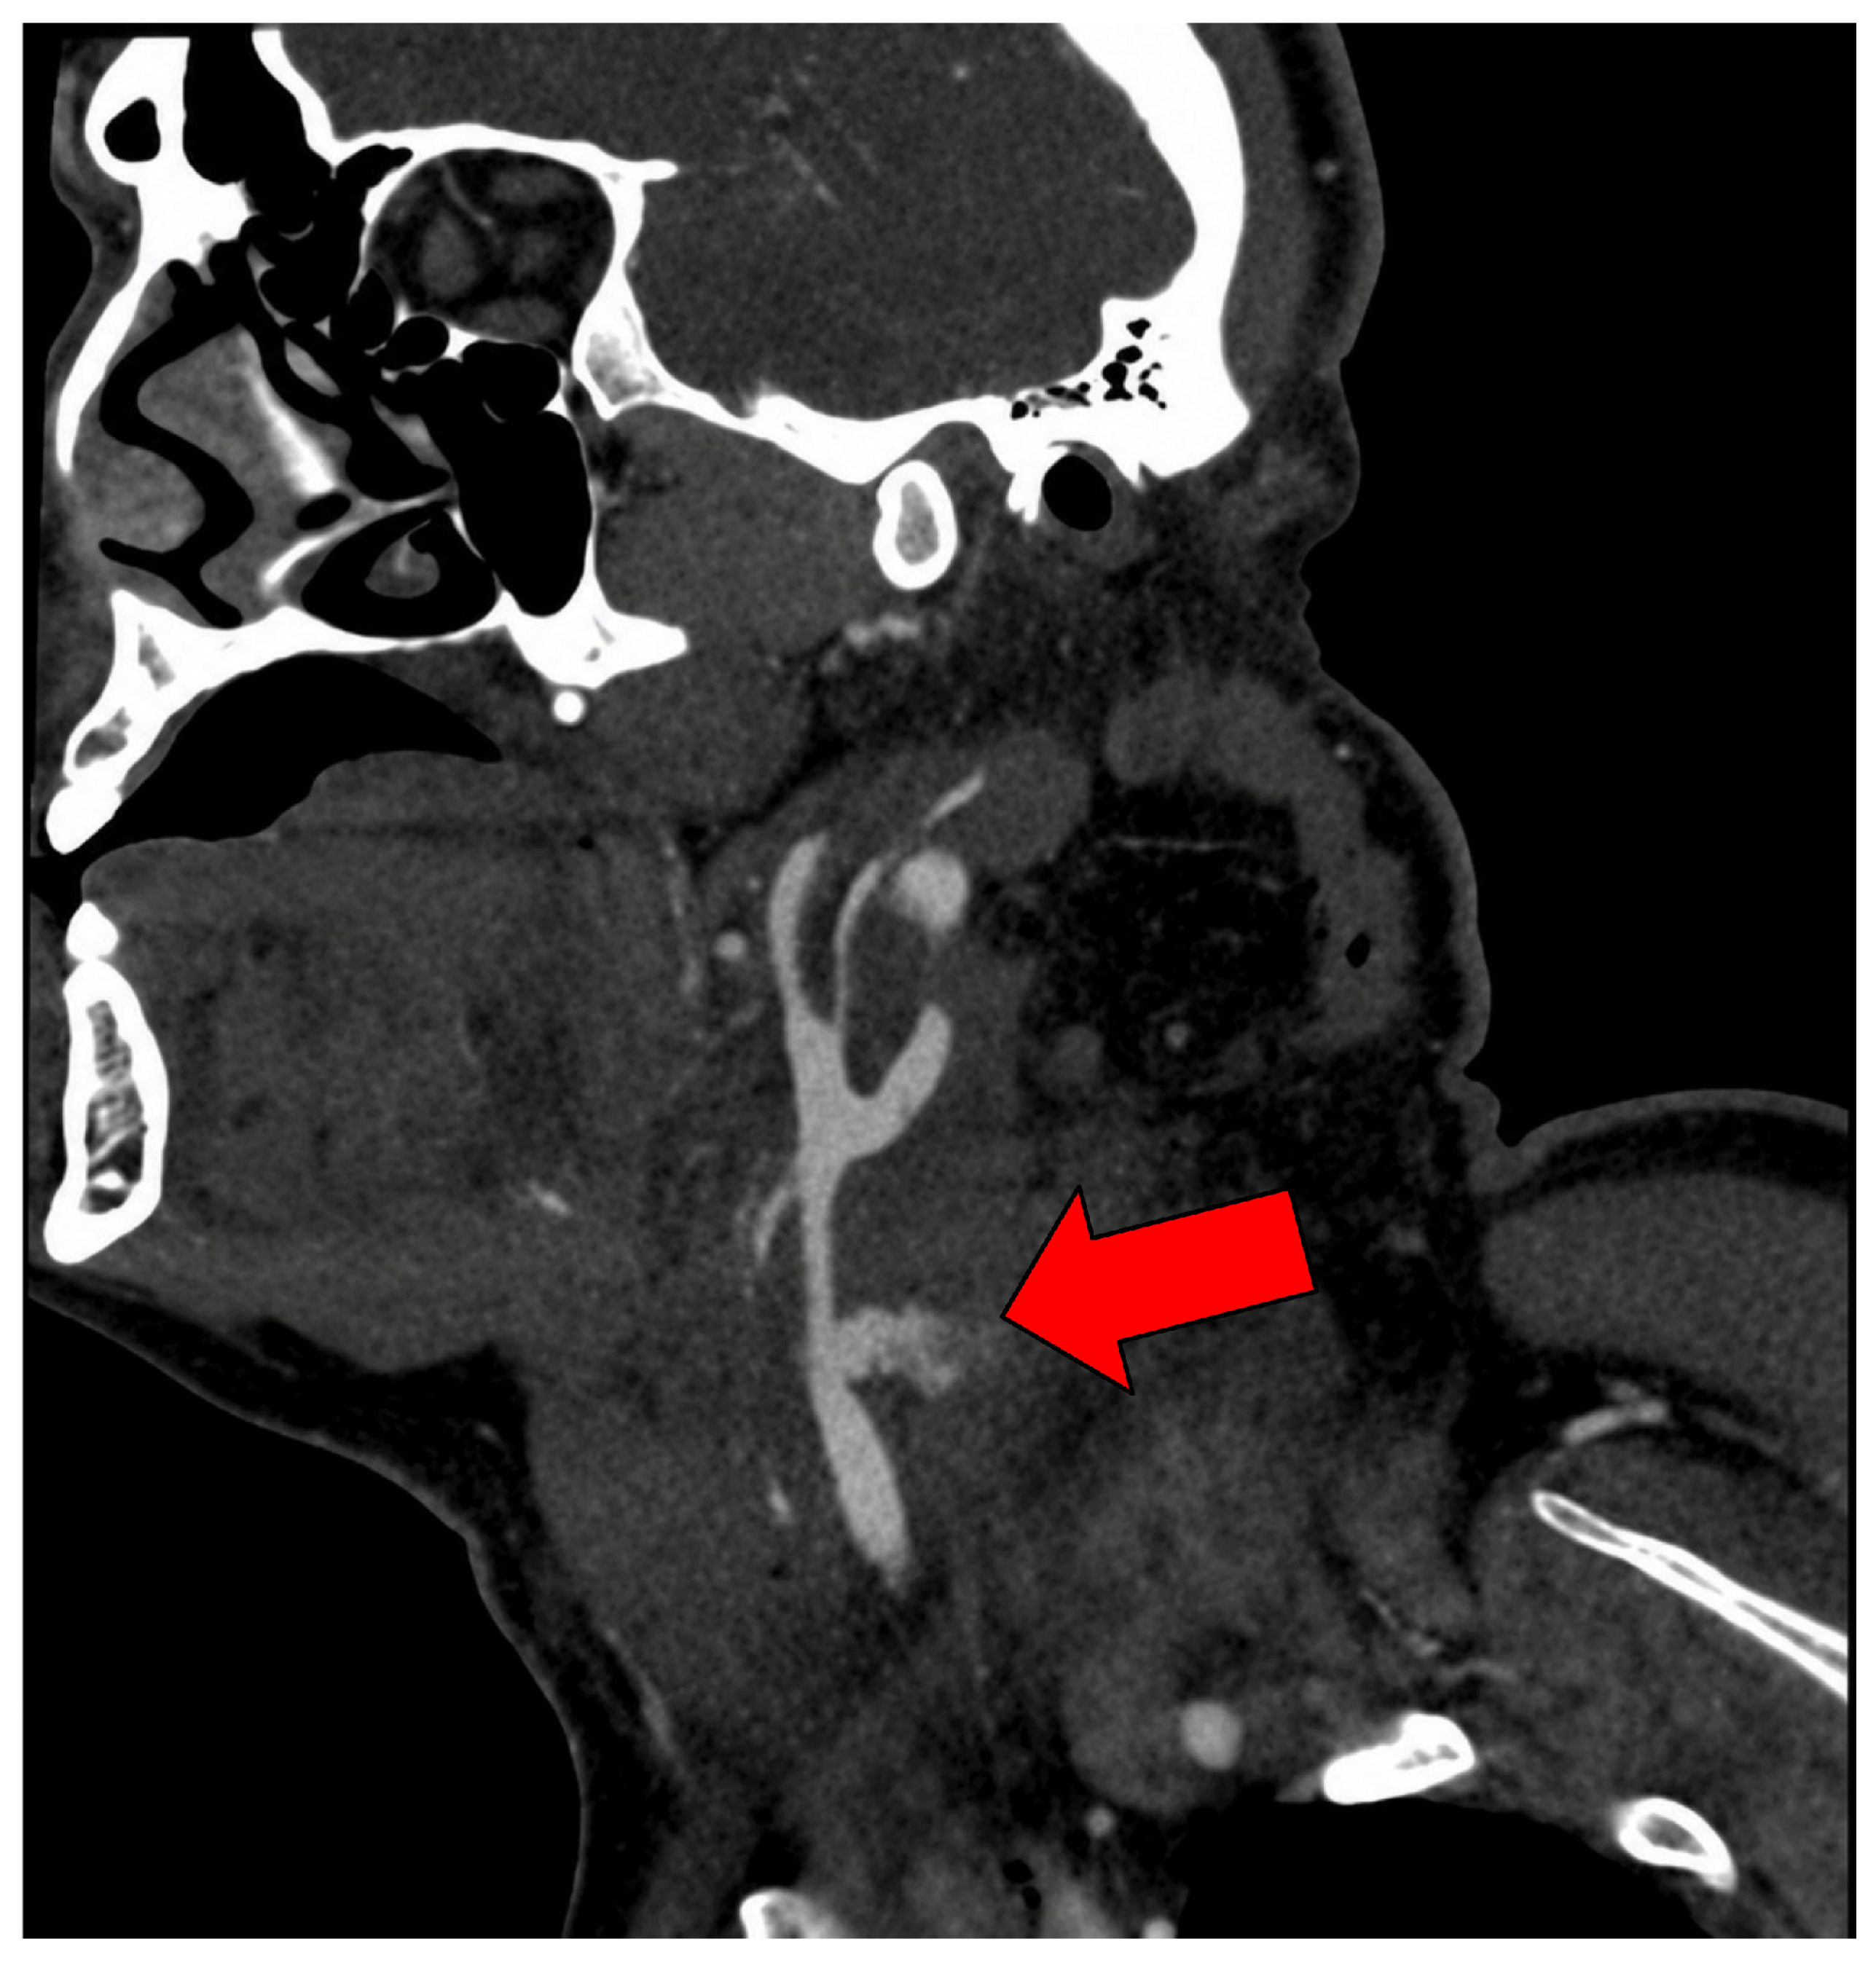
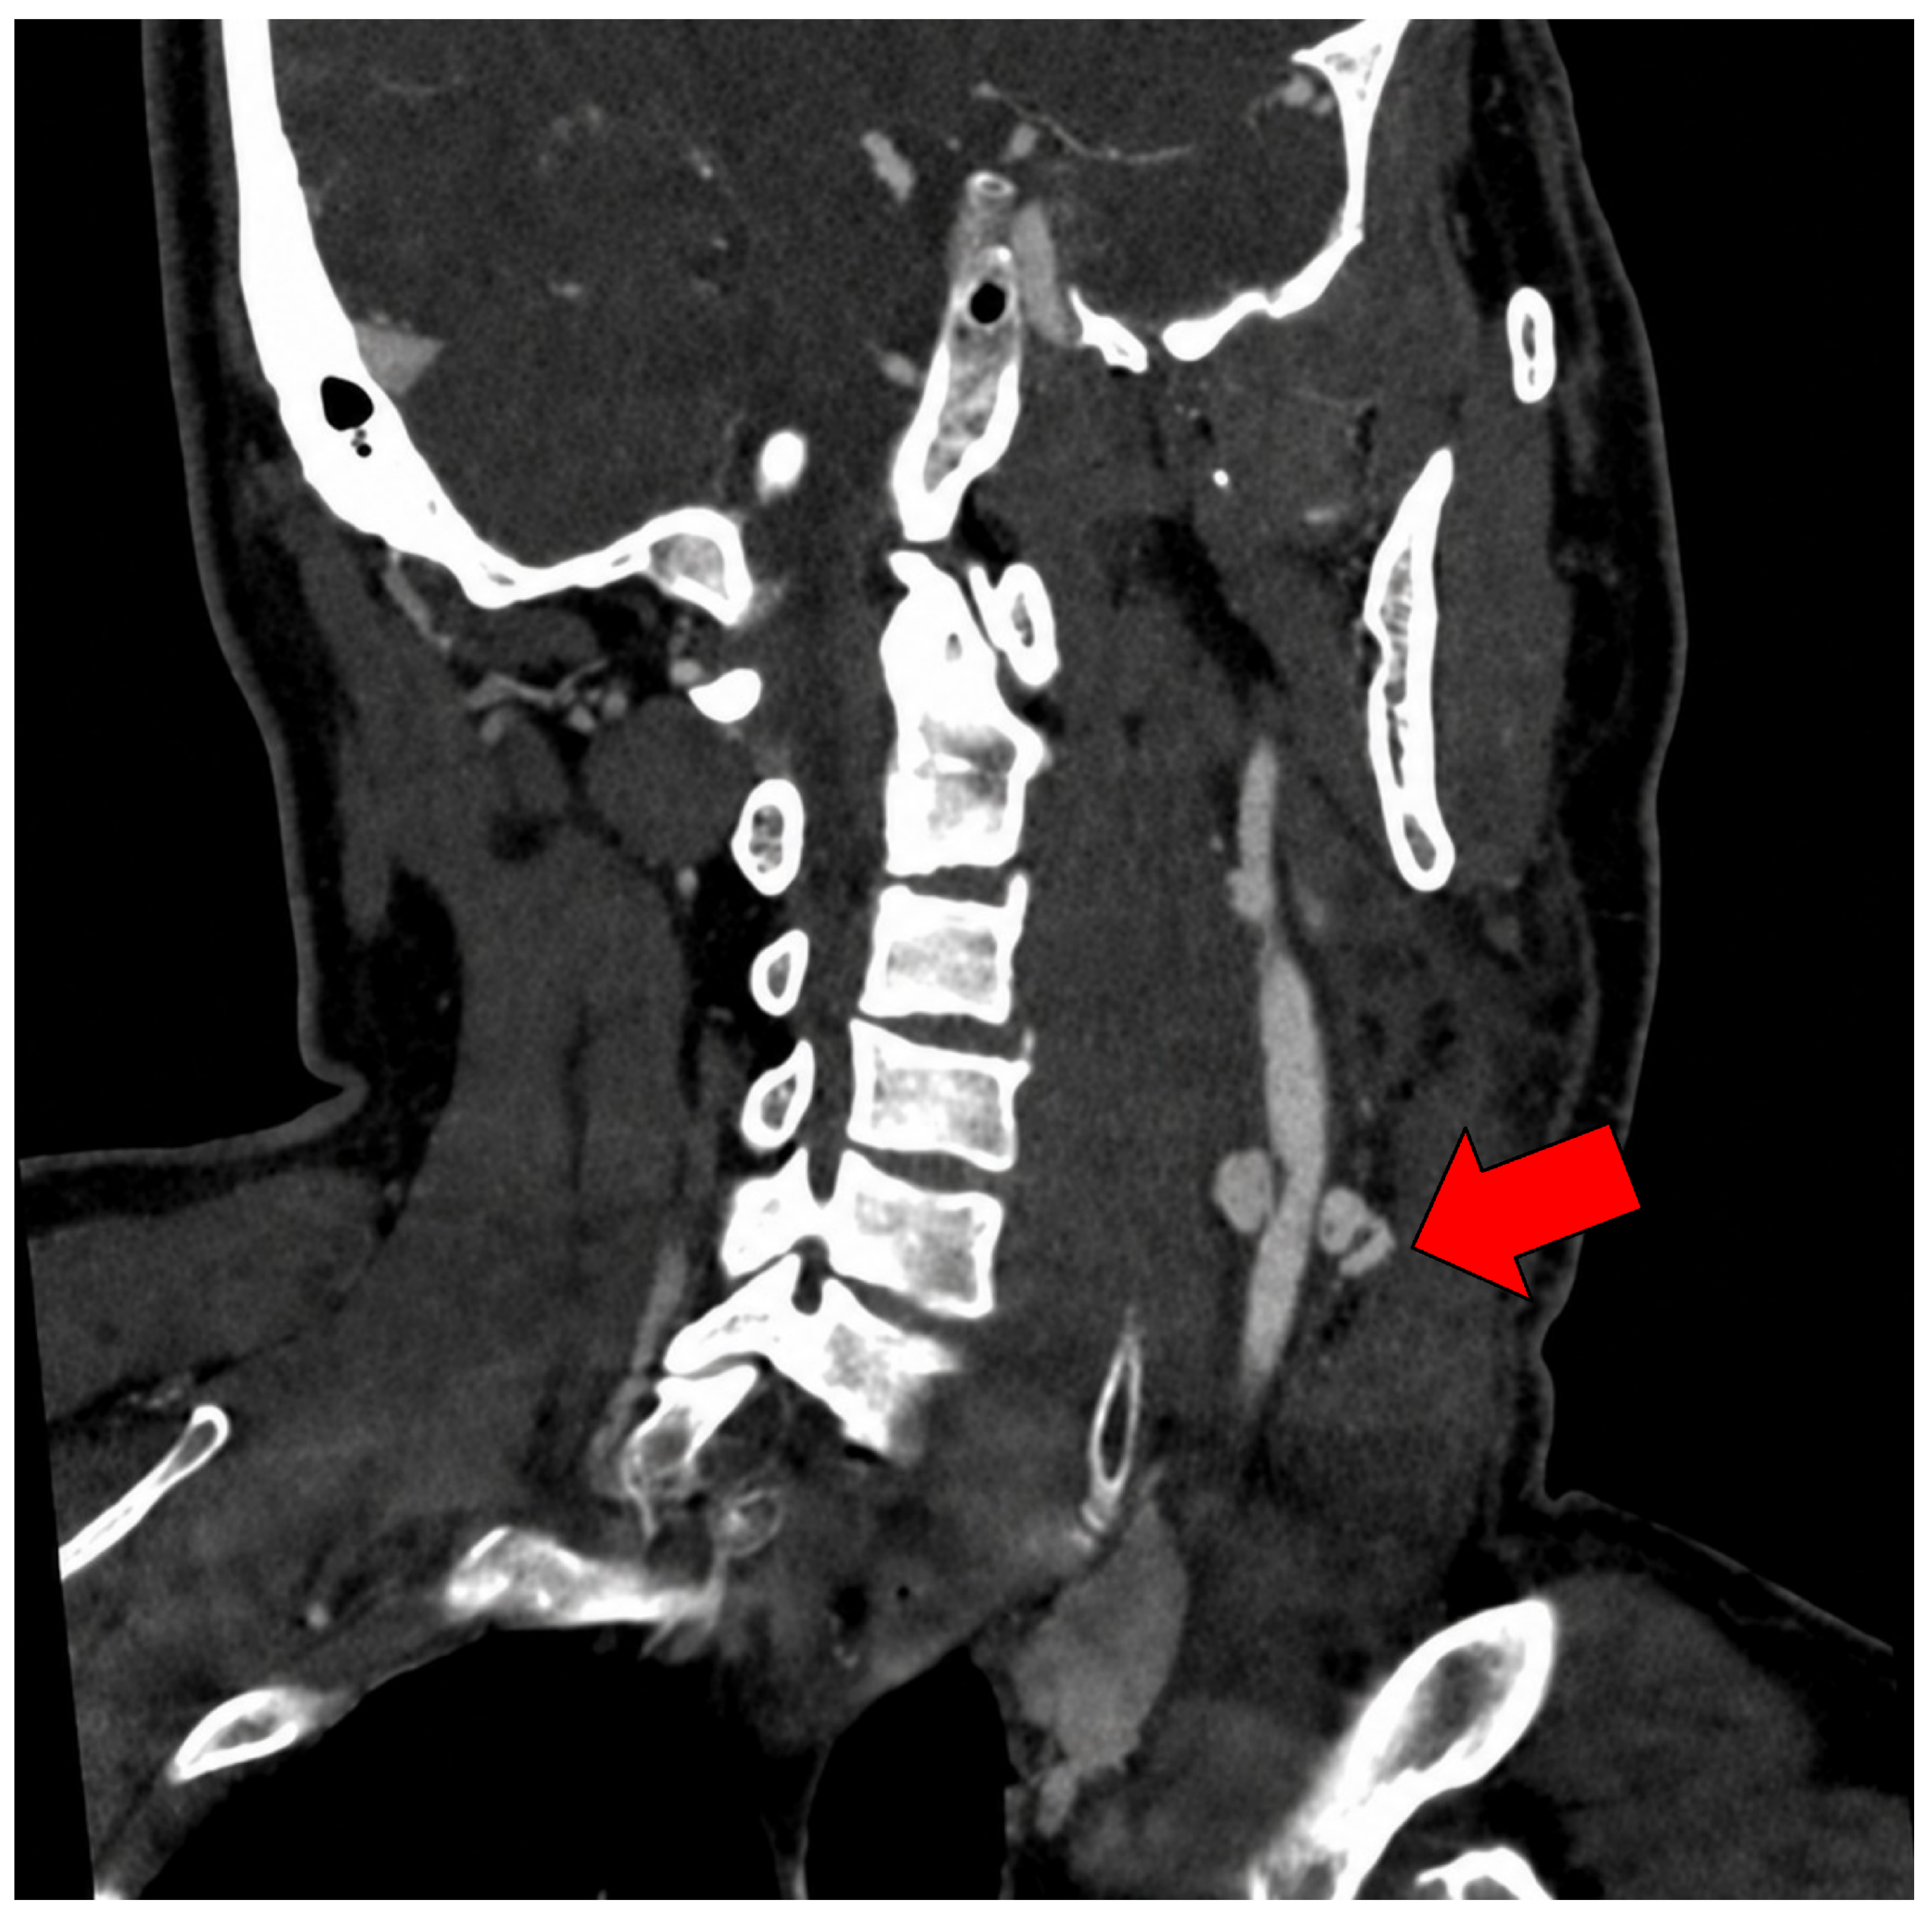
Because of the penetrating mechanism and the proximity of the wound tract to major vascular structures, computed tomography angiography was performed. CTA demonstrated hyperdense foci measuring 11, 12, and 17 mm adjacent to the LCCA, within the scalene muscles, and between the LCCA and the LIJV. These findings were consistent with traumatic vascular injury and active contrast extravasation. The direction of contrast extravasation toward the adjacent LIJV raised suspicion of an associated carotid–jugular AVF, although a definite fistulous communication was not unequivocally demonstrated on CTA (Figure 1). In addition, CTA demonstrated a fracture of the left zygapophysis of the fifth cervical vertebra with small metallic foreign bodies measuring approximately 4–5 mm. An area measuring 35 × 27 mm surrounded by small metallic fragments and extending toward the subcutaneous tissue, was consistent with a post-traumatic hematoma. A contrast-filled lesion adjacent to the LCCA was interpreted as a pseudoaneurysm (Figure 2).
CTA provided two clinically important diagnostic findings. First, it demonstrated that the injury was not confined to the superficial wound tract despite the patient’s stable condition and the absence of active external bleeding. Second, it defined the spatial relationship between the traumatic tract, hematoma, LCCA, LIJV, metallic fragments and cervical vertebral injury. This information raised suspicion of a combined arterial lesion with possible arteriovenous communication and provided the anatomical basis for further vascular assessment and treatment planning.
DUS revealed a hematoma with internal liquefaction adjacent to the LCCA, measuring 26 × 16 × 30 mm. Within this area, a defect in the arterial wall measuring 4.4 × 1.7 mm was identified, with no evidence of active bleeding into the hematoma. A 60% stenosis of the LCCA was also observed, resulting from mass effect exerted by the hematoma. DUS therefore complemented CTA by demonstrating the arterial wall defect and the local effect of the hematoma on the carotid lumen.
The patient underwent orthopedic and neurosurgical consultations, which deemed them not eligible for surgical intervention. Based on the clinical presentation, CTA, and DUS findings, a traumatic AVF between the LCCA and LIJV was suspected, together with a concomitant pseudoaneurysm of the LCCA. The patient was admitted to the Department of Vascular Surgery and Transplantation, University Clinical Hospital of the Medical University of Białystok for endovascular closure of the fistula.

2.3. Endovascular Treatment

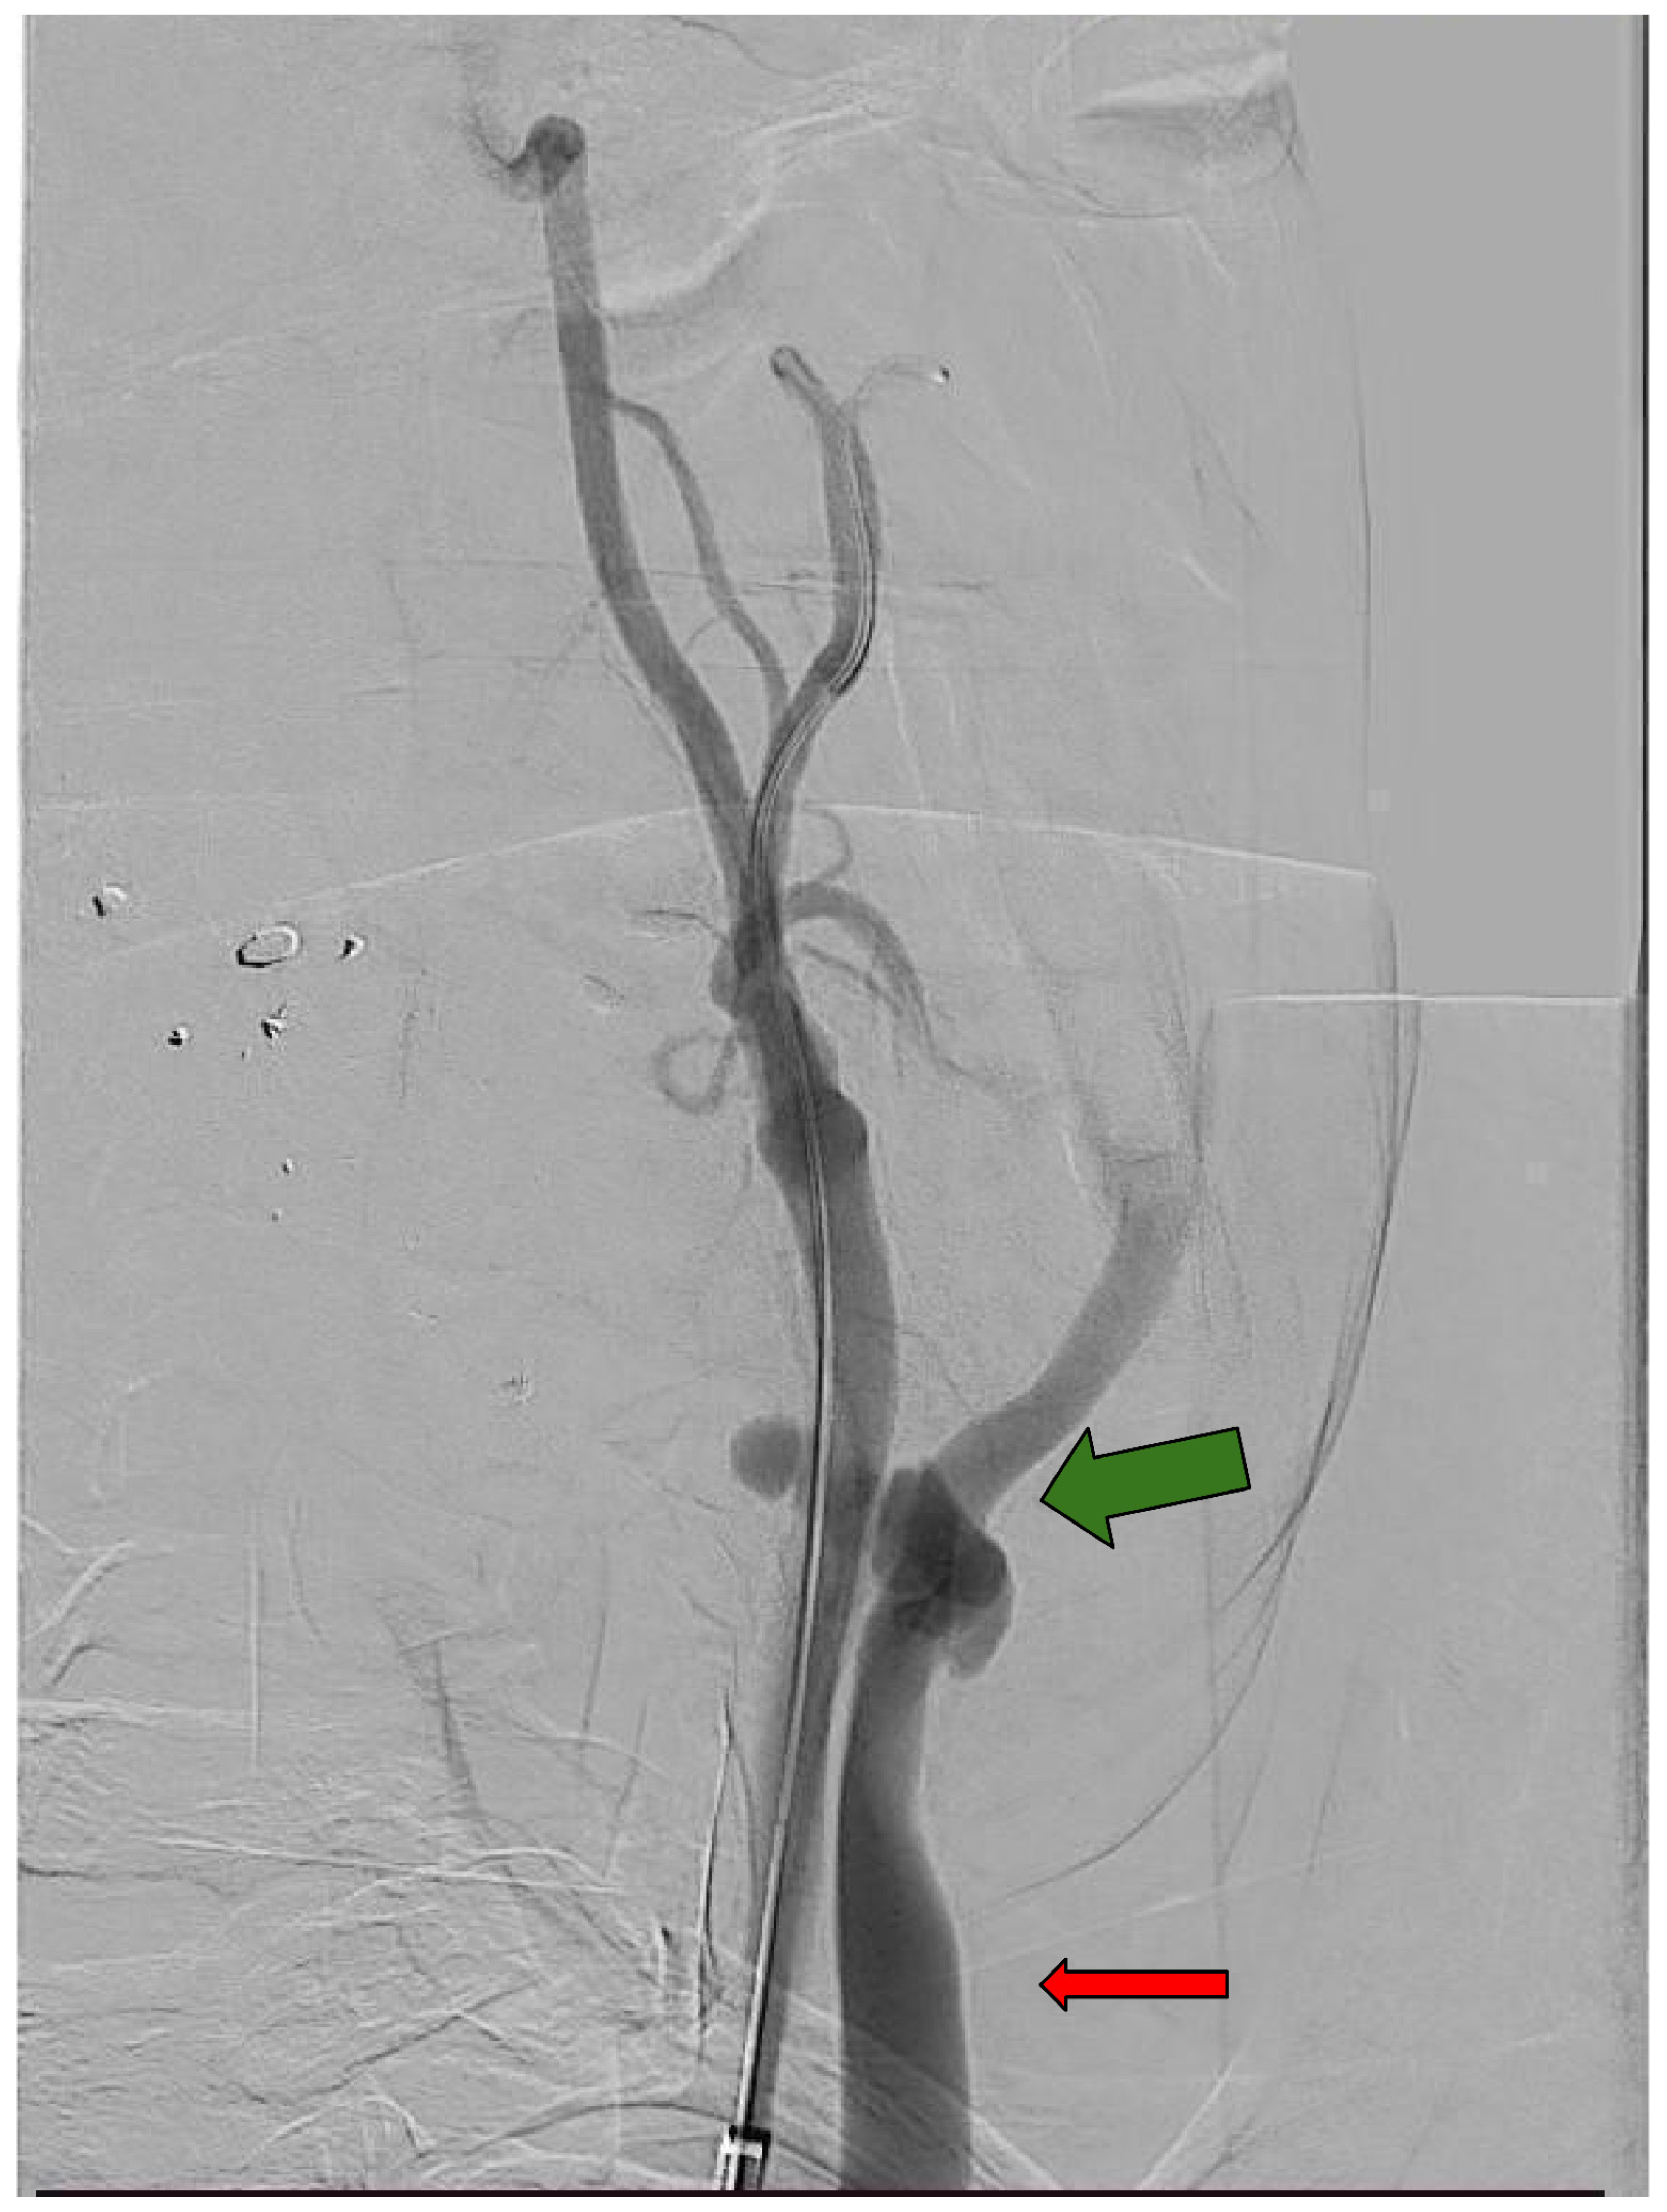
The procedure was performed under local anesthesia at the right femoral access site. Selective DSA of the LCCA confirmed an AVF between the LCCA and LIJV with early opacification of the venous system and demonstrated a concomitant LCCA pseudoaneurysm (Figure 3). DSA provided dynamic information that could not be fully obtained from static cross-sectional imaging alone: it confirmed the direction and timing of contrast passage from the arterial to the venous system, identified the parent artery, demonstrated the relationship between the pseudoaneurysm and fistulous communication and allowed assessment of the available landing zones.
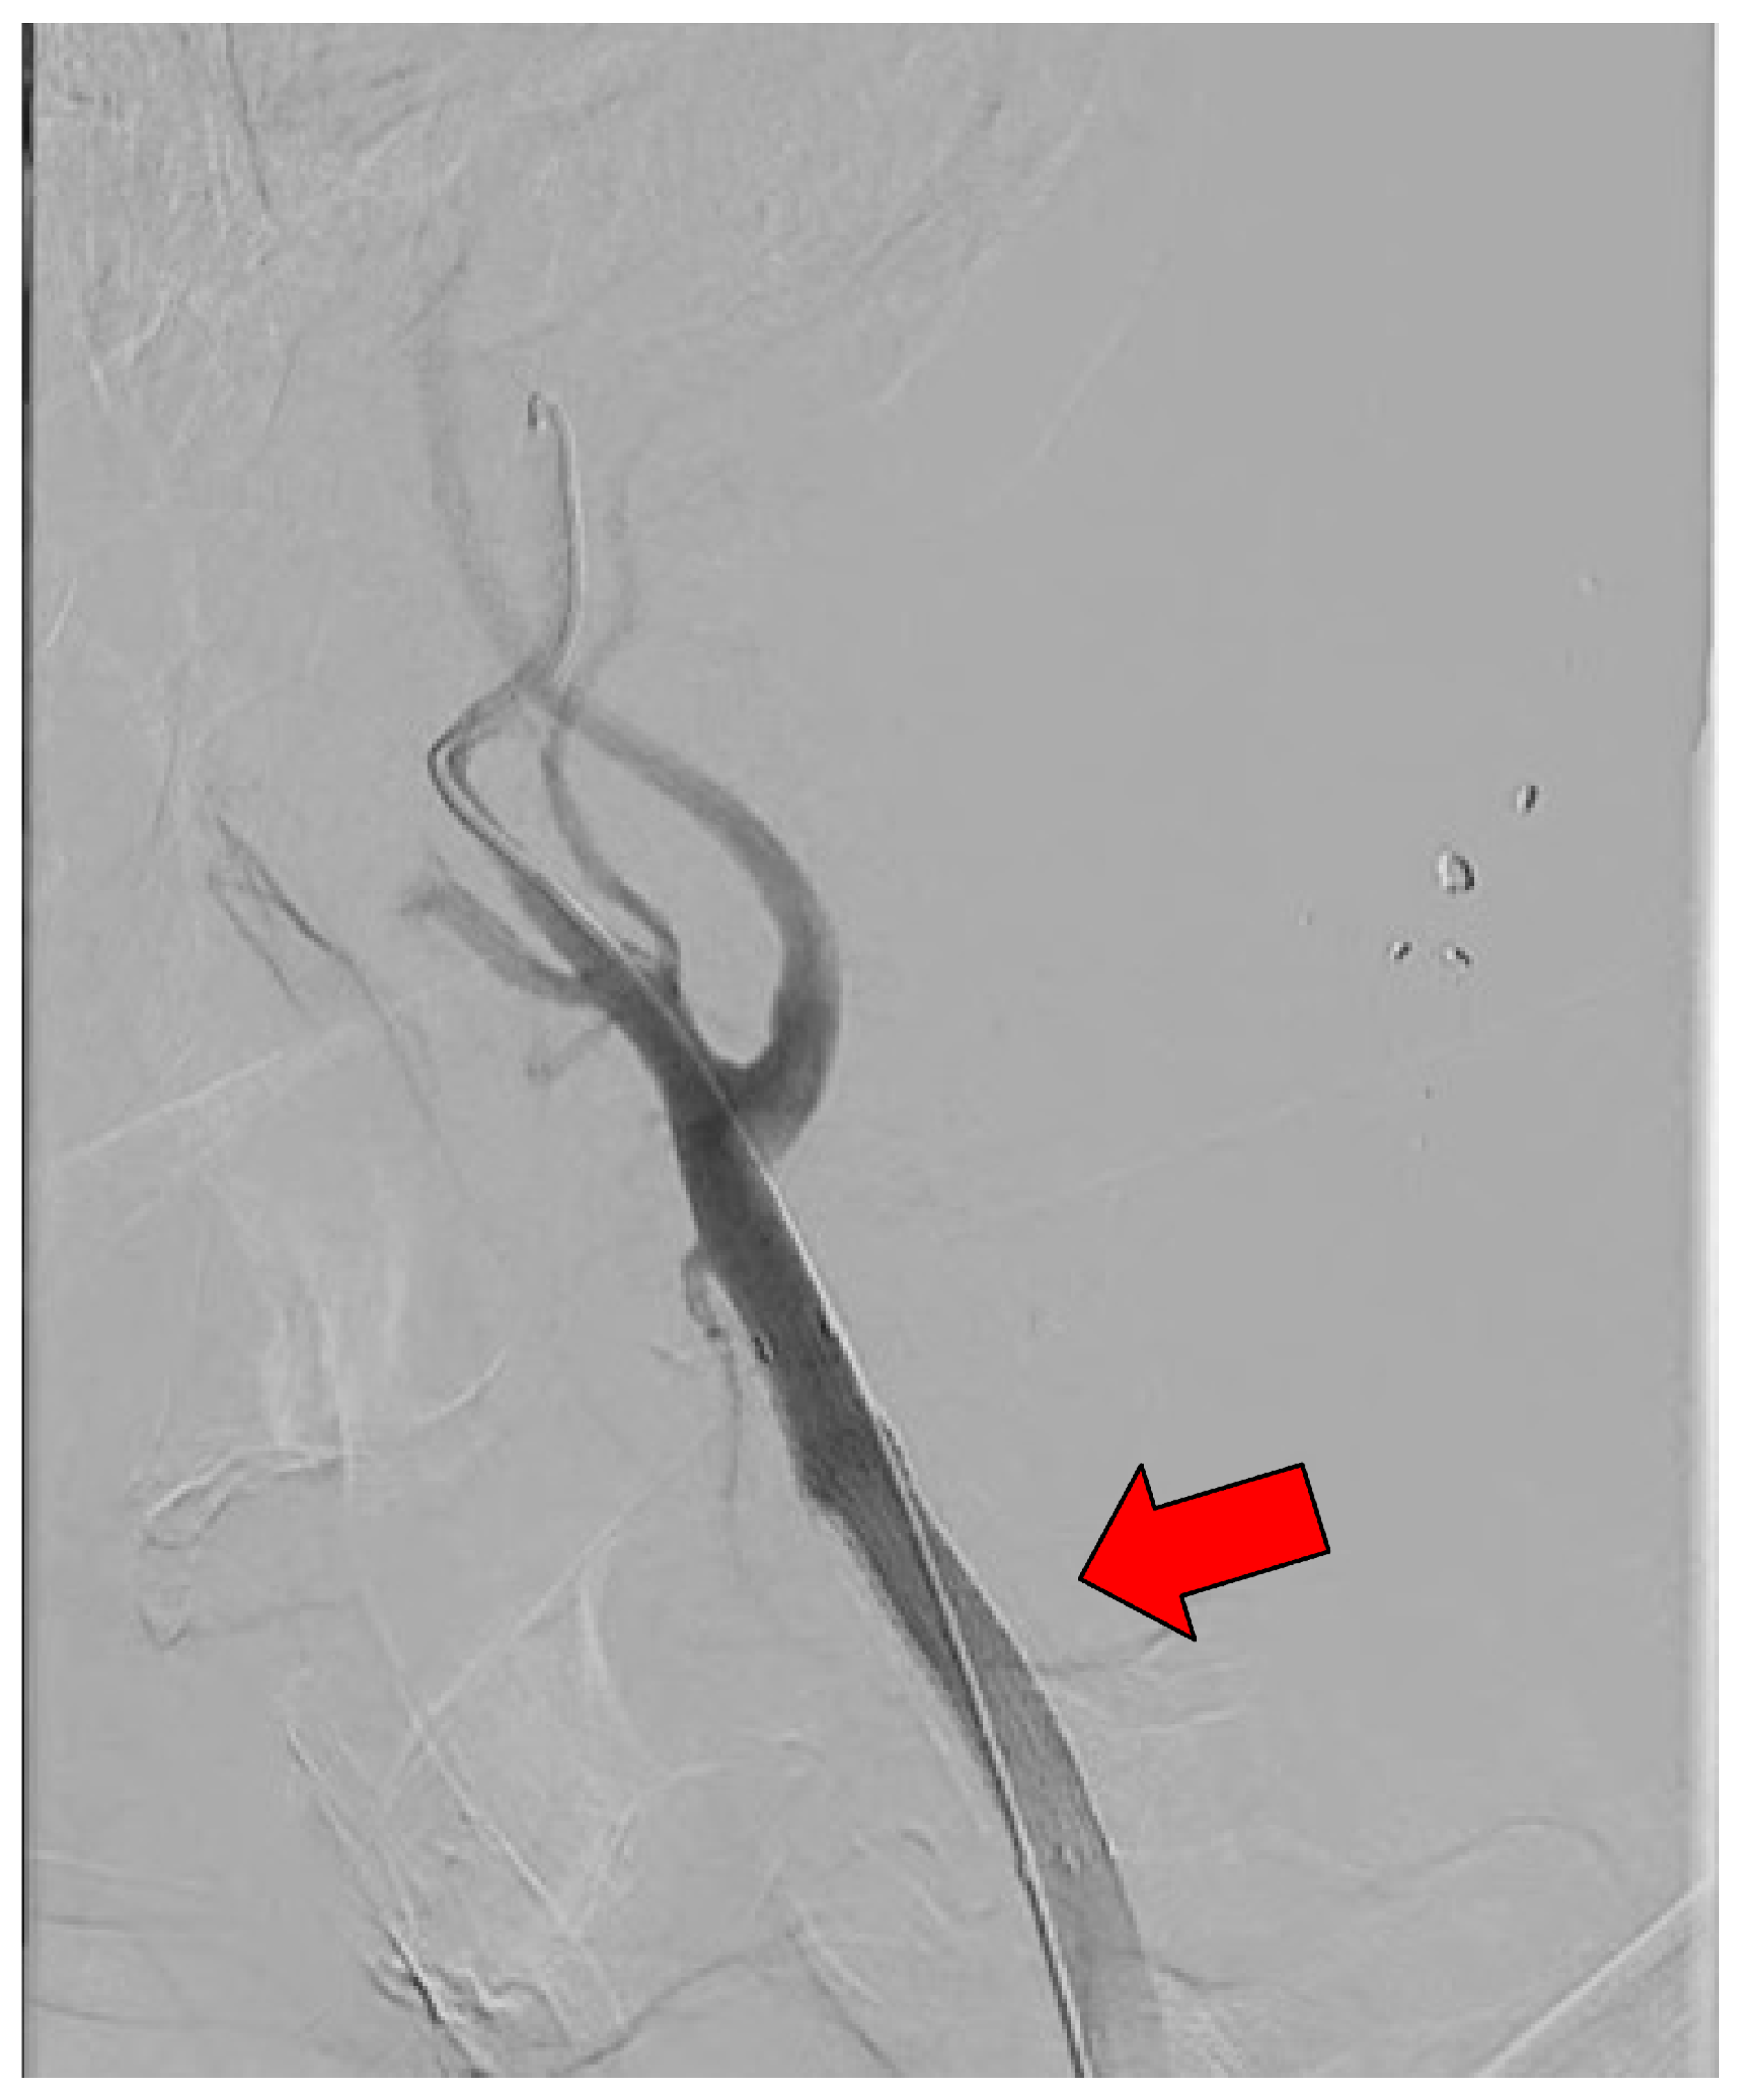
A Gore Viabahn covered stent-graft was implanted, with distal anchoring at the level of the bifurcation of the common carotid artery. The objective was to cover the arterial wall defect, close the fistulous communication and exclude the pseudoaneurysm while preserving antegrade flow through the LCCA and carotid bifurcation. The angiographic result after deployment was satisfactory and additional balloon moulding was not required. Completion angiography confirmed exclusion of both the AVF and pseudoaneurysm with preserved arterial patency (Figure 4). Cerebral protection was used during the intervention. The right femoral artery puncture site was closed using an AngioSeal device.

2.4. Postprocedural Course

Because of the penetrating mechanism of injury and the presence of retained metallic fragments, antibiotic therapy was administered during hospitalization. The postprocedural course was uncomplicated. After two days of hospitalization, the patient was discharged with a recommendation for dual antiplatelet therapy. Unfortunately, the patient did not attend the scheduled follow-up visit and long-term clinical or imaging observation was not possible.

3. Discussion

The present case demonstrates several clinically important aspects of post-traumatic cervical vascular injury. First, a clinically stable presentation does not exclude significant vascular damage after penetrating neck trauma [11,12,14,15,16]. Second, arteriovenous fistula and pseudoaneurysm may coexist after gunshot injury when both the arterial wall and adjacent venous structures are involved [2,8,9,10,20]. Third, computed tomography angiography and angiography are complementary diagnostic tools: computed tomography angiography identifies the lesion and associated traumatic findings, whereas angiography confirms the hemodynamics of the fistula and enables immediate endovascular treatment planning [11,12,14,15,18,19]. Finally, covered stent-graft implantation may be an effective reconstructive treatment strategy in selected patients, allowing closure of the fistula and pseudoaneurysm while preserving the parent artery [9,10,17,18,19,20,21,22,23,24].
Post-traumatic arteriovenous fistulas are rare but well-recognized sequelae of penetrating vascular injury [2,3,4]. A collective review of traumatic penetrating arteriovenous fistulas emphasized that the condition is uncommon and that diagnosis may be delayed, particularly when early clinical manifestations are nonspecific [2]. Series and case reports show that traumatic arteriovenous fistulas can affect different anatomical regions, including the extremities, abdomen, pelvis, thorax and neck [2,3,4,5,6].
Cervical carotid-jugular fistulas are particularly uncommon. A reported incidence of approximately 4–7% of all traumatic arteriovenous fistulas has been cited for post-traumatic common carotid artery-internal jugular vein fistulas [25]. Sinha et al. described a delayed traumatic common carotid artery-internal jugular vein fistula presenting with life-threatening epistaxis, illustrating that such lesions may remain undiagnosed for prolonged periods and later present with severe complications [25]. Nawrocki et al. reported delayed presentation of a carotid-jugular fistula after blunt injury from an arrow, again emphasizing that cervical arteriovenous fistulas may present after the acute trauma phase and with symptoms not limited to the neck [26]. Other reports also show that traumatic carotid-jugular fistulas may present with atypical or delayed manifestations, including neuro-ophthalmic symptoms, forensic implications after stab injury and complex combined carotid lesions after penetrating trauma [17,27,28,29]. These observations support a key message of the present case: the absence of massive bleeding at presentation should not lower diagnostic vigilance when the trajectory of a penetrating injury passes near major vessels [11,12,14,15,25,26,30].
Pseudoaneurysm formation represents another important diagnostic consideration. The mechanism involves disruption of the arterial wall with persistent communication between the arterial lumen and a contained extravascular cavity. In the setting of penetrating trauma, a pseudoaneurysm may be detected early as active extravasation or as a contrast-filled sac, or later as an enlarging pulsatile lesion [8,10]. When the pseudoaneurysm extends toward or communicates with an adjacent vein, a combined pseudoaneurysm and arteriovenous fistula may develop [2,8,9,10,20]. This combination has been reported in other vascular territories, including iliac vessels after gunshot trauma, and it is especially important diagnostically because the fistulous component may change flow dynamics and obscure the interpretation of hematoma or pseudoaneurysm on single-phase imaging [9,20].
The diagnostic pathway in this case reflects the current trend in the management of penetrating neck trauma [11,12,14,15,16]. Traditional management relied heavily on anatomical zones of injury. Contemporary approaches increasingly use a “no-zone” strategy in stable patients, with computed tomography angiography serving as the principal screening tool when vascular or aerodigestive injury is suspected [11,12,14,15]. Ibraheem et al. reviewed computed tomography angiography in the no-zone approach and found that it provides reliable diagnostic performance for detecting injuries in stable patients with penetrating neck trauma [11]. Paladino et al. systematically reviewed computed tomography angiography for aerodigestive injuries in penetrating neck trauma, further supporting its role in modern diagnostic pathways while also emphasizing that clinical context remains important [14]. Recent reviews of penetrating neck trauma similarly support structured evaluation based on hemodynamic stability, hard signs, soft signs, trajectory, and cross-sectional vascular imaging [12,15,16].
In the present case, computed tomography angiography was decisive for three reasons. First, it detected deep vascular abnormalities despite the absence of active external bleeding. Second, it demonstrated the topographic relationship between the bullet tract, hematoma, left common carotid artery, left internal jugular vein, metallic foreign bodies, and cervical vertebral injury. Third, it provided the anatomical basis for selecting an endovascular approach [11,12,14,15,18,19]. These are important diagnostic insights for clinicians and radiologists: in penetrating neck trauma, the external wound size may underestimate the extent of internal injury; a stable patient may still harbor a lesion requiring urgent specialist management; and vascular imaging can transform an apparently limited soft-tissue injury into a clearly defined arterial and arteriovenous pathology requiring intervention [11,12,14,15,16].
Doppler ultrasonography also contributed to the diagnostic assessment. In arteriovenous fistulas, Doppler ultrasonography may demonstrate turbulent flow, arterialized venous waveform, low-resistance arterial waveform, and direct communication between vessels [1,3]. In pseudoaneurysm, it may show the characteristic “yin-yang” flow pattern within the sac and a “to-and-fro” waveform at the neck [8,10]. However, ultrasonography is operator-dependent and may be limited in penetrating neck trauma by pain, hematoma, air, metallic fragments, wound dressings, and difficult acoustic windows [11,12,14,15,16]. In this case, ultrasonography confirmed a hematoma adjacent to the left common carotid artery and demonstrated an arterial wall defect, but computed tomography angiography and angiography were more important for defining the complete vascular lesion and treatment strategy [11,12,14,15,18,19].
In the present case, CTA demonstrated traumatic arterial injury and contrast extravasation directed toward the adjacent LIJV, raising suspicion of an associated carotid-jugular AVF. However, the fistulous communication and unequivocal early venous opacification were not directly demonstrated on the available CTA images. This may have been related to the timing of contrast acquisition, the small size or configuration of the fistulous tract, and partial obscuration by the adjacent hematoma and artifacts from retained metallic fragments. DUS demonstrated the arterial wall defect and local compression of the LCCA but did not unequivocally show arteriovenous shunting, potentially because of the deep location of the lesion and the restricted acoustic window. Selective DSA, owing to its high temporal resolution and dynamic visualization of contrast flow, confirmed the AVF by demonstrating rapid contrast passage from the LCCA into the LIJV with early venous opacification. DSA also confirmed the concomitant pseudoaneurysm and allowed precise placement of the covered stent-graft across the arterial defect. Completion angiography subsequently verified closure of the AVF and exclusion of the pseudoaneurysm, with preserved LCCA patency. This immediate pre- and post-treatment confirmation is particularly important in cervical lesions, where persistent endoleak or incomplete fistula closure could result in continued risk of bleeding, venous hypertension, embolic complications, or recurrent symptoms [5,9,10,17,18,19,20,21,22,23].
The treatment of traumatic arteriovenous fistulas should be individualized. Open surgical repair may include ligation and division of the fistula, direct arterial repair, patch angioplasty, interposition grafting, bypass, or venous repair [2,4,5]. Surgery remains necessary in unstable patients, contaminated wounds, failed endovascular treatment, infected lesions, or when the anatomy is unsuitable for stent placement [2,5,15]. However, the cervical region poses specific surgical difficulties. Exposure of the common carotid artery and internal jugular vein may be complicated by hematoma, inflammation, scar tissue, proximity of cranial nerves, risk of major bleeding, and the need to preserve cerebral perfusion [15,16,17]. These factors explain why endovascular treatment is increasingly considered in selected stable patients [5,9,10,17,18,19,20,21,22,23].
Endovascular options include coil embolization, detachable balloons, vascular plugs, bare stents, stent-assisted coiling, and covered stent-grafts [5,9,18,19,22,23]. The choice depends on lesion morphology, parent vessel importance, fistula size, landing zones, arterial diameter, tortuosity, and the need to preserve flow [5,9,10,18,19]. In lesions involving major arteries such as the common carotid artery, preserving the parent artery is often desirable [9,10,17,18,19]. Covered stent-grafts provide a reconstructive solution because they create a barrier between the arterial lumen and the injured wall, excluding the pseudoaneurysm and sealing the arteriovenous communication while maintaining flow through the carotid artery [9,10,17,18,19,20,21,22,23].
Several reports support the feasibility of covered stenting for traumatic carotid pseudoaneurysm [9,10,18,19,31]. Wang et al. reported satisfactory procedural and long-term outcomes after covered stenting for traumatic carotid pseudoaneurysm, with complete exclusion of the pseudoaneurysm and preservation of parent artery patency in their series [9]. Jariwala et al. described endovascular management of post-traumatic common carotid artery pseudoaneurysms after high-velocity fragment injuries and emphasized the value of multidetector computed tomography angiography in diagnosis and treatment planning [10]. Abdelsalam et al. reported use of a balloon-mounted covered stent for traumatic cervical internal carotid artery pseudoaneurysm, illustrating continued expansion of endovascular options for traumatic cervical carotid lesions [18]. Singh et al. also described covered stent treatment for post-traumatic internal carotid artery pseudoaneurysm, supporting the growing experience with endovascular reconstruction in such injuries [19].
The present case adds to the literature because it combines several uncommon features in one patient: gunshot-related penetrating neck trauma, cervical arteriovenous fistula involving the left common carotid artery and left internal jugular vein, concomitant pseudoaneurysm of the left common carotid artery, and successful exclusion of both lesions using a covered stent-graft [9,10,20,25,26,32,33]. Many published reports focus either on isolated pseudoaneurysm or isolated arteriovenous fistula [18,19]. Reports combining both lesions after penetrating trauma are less frequent, and cervical carotid-jugular involvement is particularly rare [20,25,26,32,33]. This case therefore supports the importance of carefully evaluating for both pseudoaneurysm and arteriovenous communication when vascular injury is suspected after penetrating neck trauma [11,12,14,15,16].
Another important aspect is the role of imaging in selecting the treatment method [10,11,12,14,15]. Without vascular imaging, the apparently limited external injury could have led to underestimation of the underlying vascular damage. CTA established the diagnosis and enabled prompt referral for definitive treatment [11,12,14,15,16]. Conversely, computed tomography angiography and angiography allowed identification of a lesion suitable for endovascular reconstruction [9,10,18,19]. The ability to define proximal and distal landing zones is essential before covered stent-graft placement [9,10,17,18,19]. Inadequate landing zones, excessive tortuosity, branch coverage, vessel size mismatch, or infection may limit the use of this technique [9,17,18,19]. In the present case, angiography allowed precise deployment with distal anchoring at the level of the common carotid artery bifurcation and immediate confirmation of technical success.
The diagnostic and therapeutic strategy must also consider postprocedural management. Covered stents in carotid arteries require attention to antiplatelet therapy, stent patency, thrombotic risk, endoleak, restenosis, and recurrent pseudoaneurysm or fistula [9,17,18,19,23]. Dual antiplatelet therapy was recommended in this patient after discharge.
From a broader diagnostic perspective, the case supports several practical recommendations. In penetrating neck trauma, clinicians should maintain suspicion for vascular injury even when external wounds are small and the patient is hemodynamically stable. Computed tomography angiography should be considered when the wound trajectory approaches major vessels or when physical examination reveals swelling, hematoma, bruit, thrill, neurological symptoms, bleeding, or unexplained pain [11,12,14,15,16]. Radiologists should actively assess for direct and indirect signs of arteriovenous fistula, including early venous opacification, abnormal communication between adjacent vessels, pseudoaneurysm, contrast extravasation, hematoma, vessel narrowing, and retained foreign bodies [1,8,10,11,12,14,15]. When computed tomography angiography suggests a complex lesion, selective catheter angiography may provide definitive confirmation and a route to immediate treatment [5,9,10,18,19].
The review of the literature indicates that current evidence for traumatic arteriovenous fistulas and carotid pseudoaneurysms is based mainly on case reports, case series and retrospective reviews [2,4,5,9,10,17,18,19]. Randomized trials are not feasible in such rare and heterogeneous traumatic conditions. Therefore, detailed case reports remain valuable when they include clear imaging documentation, treatment rationale and discussion of how the case adds to existing knowledge [9,10,18,19,20,25,26,32,33]. The current case contributes by documenting the imaging pathway and endovascular management of a rare combined cervical lesion after gunshot injury. It also reinforces that the diagnostic work-up should not stop after identifying a hematoma; instead the possibility of pseudoaneurysm and arteriovenous fistula should be actively excluded [8,10,11,12,14,15,16].
The main limitation of this report is the absence of long-term clinical and imaging follow-up, as the patient did not attend the scheduled follow-up visit. Therefore, only immediate technical success and an uncomplicated short-term hospital course could be documented, whereas long-term stent-graft patency and durability of lesion exclusion could not be assessed. Furthermore, because the case was reviewed retrospectively, the available records did not permit reliable retrieval of the precise diagnostic and treatment time intervals, detailed vascular and landing-zone measurements, exact stent-graft and sheath dimensions, procedural and fluoroscopy times, radiation dose, contrast volume, or information on whether the cervical hematoma underwent separate evacuation. These parameters were therefore not estimated or retrospectively reconstructed.

4. Conclusions

This case illustrates that penetrating neck trauma may result in a complex vascular injury combining an arteriovenous fistula and pseudoaneurysm. Owing to the complex cervical anatomy and proximity of critical structures, accurate imaging assessment is essential.
In hemodynamically stable patients, CTA supports the identification and anatomical characterization of vascular injury, whereas DUS and DSA may provide complementary information for lesion assessment and procedural planning. In the present case, DSA confirmed arteriovenous shunting and enabled endovascular treatment.
Covered stent-graft implantation achieved immediate technical exclusion of both lesions with preserved LCCA patency. This case supports the procedural feasibility of this approach in carefully selected patients; however, the absence of long-term follow-up precludes conclusions regarding treatment durability. Appropriate antiplatelet therapy and structured imaging surveillance are required.

Author Contributions

The requirements for authorship have been met; each author believes that the manuscript represents honest work. M.C. (Michał Chlabicz) and Ł.S. conceptualized the manuscript, collected the clinical data, performed the literature review, and drafted the initial version of the manuscript. M.C. (Michał Chlabicz), M.J. and J.G. were involved in the clinical management of the patient and critically revised the manuscript for important intellectual content. M.C. (Maciej Chlabicz) contributed to the interpretation of imaging and procedural findings. All authors have read and agreed to the published version of the manuscript.

Funding

This research received no external funding.

Institutional Review Board Statement

This report describes a single clinical case and did not involve any experimental intervention. The case was prepared in accordance with the ethical principles of the Declaration of Helsinki.

Informed Consent Statement

Written informed consent has been obtained from the patient to publish this paper.

Data Availability Statement

The data presented in this case report are available from the corresponding author on reasonable request. The data are not publicly available owing to patient privacy and data-protection restrictions.

Conflicts of Interest

The authors declare that they have no competing interests.

References

  1. Jayroe, H.; Foley, K. Arteriovenous Fistula. In StatPearls [Internet]; StatPearls Publishing: Treasure Island, FL, USA, 2026. Available online: https://www.ncbi.nlm.nih.gov/books/NBK559213/ (accessed on 5 May 2026).
  2. Asensio, J.A.; Dabestani, P.J.; Miljkovic, S.S.; Wenzl, F.A.; Kessler, J.J.; Kalamchi, L.D.; Kotaru, T.R.; Agrawal, D.K. Traumatic penetrating arteriovenous fistulas: A collective review. Eur. J. Trauma Emerg. Surg. 2022, 48, 775–789. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  3. Carvajal, G.; Brito, A.; Simo, E. Traumatic Arteriovenous Fistula [Internet]. In Arteriovenous Fistulas—Diagnosis and Management; InTech: London, UK, 2013. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  4. Şahin, M.; Yücel, C.; Kanber, E.M.; İlal Mert, F.T.; Bıçakhan, B. Management of traumatic arteriovenous fistulas: A tertiary academic center experience. Turk. J. Trauma Emerg. Surg. 2018, 24, 234–238. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  5. Bounssir, A.; Taghi, H.; Sedki, N.; Bakkali, T.; Lekehal, B. Technical management of traumatic arteriovenous fistula: Tips and tricks. Int. J. Surg. Case Rep. 2020, 76, 468–473. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  6. Perinjelil, V.; Maraqa, T.; Yenter, A.C.; Ohaeri, H.; Mercer, L.; Bansal, A.; Sachwani-Daswani, G. Traumatic arteriovenous fistula formation secondary to crush injury. J. Surg. Case Rep. 2018, 2018, rjy240. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  7. Borghese, O.; Pisani, A.; Sbenaglia, G.; Giudice, R. Open surgery and endovascular techniques in treatment of acute abdominal arteriovenous fistulas. Ann. Vasc. Surg. 2019, 61, 427–433. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  8. Rivera, P.A.; Dattilo, J.B. Pseudoaneurysm. In StatPearls [Internet]; StatPearls Publishing: Treasure Island, FL, USA, 2026. Available online: https://www.ncbi.nlm.nih.gov/books/NBK542244/ (accessed on 5 May 2026).
  9. Wang, K.; Peng, X.-X.; Liu, A.-F.; Zhang, Y.-Y.; Lv, J.; Xiang, L.; Liu, Y.-E.; Jiang, W.-J. Covered Stenting Is an Effective Option for Traumatic Carotid Pseudoaneurysm with Promising Long-Term Outcome. J. Korean Neurosurg. Soc. 2020, 63, 590–597. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  10. Jariwala, P.; Punjani, A.; Kamble, R. Endovascular management of the post-traumatic common carotid artery pseudoaneurysms. Pol. J. Radiol. 2021, 86, e287–e290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  11. Ibraheem, K.; Wong, S.; Smith, A.; Guidry, C.; McGrew, P.; McGinness, C.; Duchesne, J.; Taghavi, S.; Harris, C.; Schroll, R. Computed tomography angiography in the “no-zone” approach era for penetrating neck trauma: A systematic review. J. Trauma Acute Care Surg. 2020, 89, 1233–1238. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  12. Chandrananth, M.L.; Zhang, A.; Voutier, C.R.; Skandarajah, A.; Thomson, B.N.J.; Shakerian, R.; Read, D.J. ‘No zone’ approach to the management of stable penetrating neck injuries: A systematic review. ANZ J. Surg. 2021, 91, 1083–1090. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  13. Kobayashi, L.; Perkins, L.; Johnston, W.; Kurth, L.; Black, K.; Abu-Zidan, F.; Augustin, G.; Balogh, Z.J.; Biffl, W.L.; Britt, L.D.; et al. American Association for the Surgery of Trauma-World Society of Emergency Surgery Guidelines on the diagnosis and management of cervical vascular injuries. J. Trauma Acute Care Surg. 2026, 100, 509–519. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  14. Paladino, L.; Baron, B.J.; Shan, G.; Sinert, R. Computed tomography angiography for aerodigestive injuries in penetrating neck trauma: A systematic review. Acad. Emerg. Med. 2021, 28, 1160–1172. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  15. Shilston, J.; Evans, D.L.; Simons, A.; Evans, D.A. Initial management of blunt and penetrating neck trauma. BJA Educ. 2021, 21, 329–335. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  16. Loss, L.; Henry, R.; White, A.; Matsushima, K.; Barrett, C.; Lammers, D.; Schreiber, M.; Inaba, K. Penetrating neck trauma: A comprehensive review. Trauma Surg. Acute Care Open 2025, 10, e001619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  17. Rouhafza, R.; Manaviat, M.; Ghasemirad, H.; Tafti, M.F.; Hosseini, S.M. Successful Surgical Management of Traumatic Carotid-Jugular Fistula in an Afghan Patient: A Case Report. Clin. Case Rep. 2025, 13, e70816. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  18. Abdelsalam, A.; Saini, V.; Eatz, T.; Silva, M.A.; Luther, E.M.; Bandes, M.; Thompson, J.W.; Ramsay, I.A.; Burks, J.D.; Fountain, H.B.; et al. Balloon-mounted covered stent as endovascular management of a traumatic cervical internal carotid artery pseudoaneurysm in a 23-year-old: A case report. AME Case Rep. 2023, 8, 17. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  19. Singh, D.; Shankar, D.; Sharma, G.; Yadav, K.; Kaif, M. Use of covered stent (CGuard) in the treatment of post-traumatic internal carotid artery pseudoaneurysm. J. Cerebrovasc. Endovasc. Neurosurg. 2022, 24, 257–262. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  20. Akbudak, I.; Tekinhatun, M.; Duyu, M.S.; Cihan, F. Iliac Arteriovenous Fistula and Pseudoaneurysm Secondary to Gunshot Trauma. Diagnostics 2025, 15, 1882. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  21. Gao, H.; Zhou, D.; Zhou, Y.; Wu, X.; Wang, J.; Wang, Q. Traumatic facial arteriovenous fistula: A rare case report and literature review. Int. J. Emerg. Med. 2025, 18, 66. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  22. Seraj, F.Q.M.; Najafi, S.; Al Raaisi, A.; Mirbolouk, M.H.; Ebrahimnia, F.; Shamsi, H.P.; Garivani, Y.; Zabihyan, S.; Mowla, A.; Baharvahdat, H. Treatment of Traumatic Direct Carotid-Cavernous Fistula with a BeGraft-Covered Stent. Neurointervention 2024, 19, 111–117. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  23. Zhao, Y.; Liu, Z.; Sun, R.; Pan, L.; Yang, M.; Song, J.; Ma, L. The Clinical Efficacy Analysis of Treatment with a Willis Covered Stent in Traumatic Pseudoaneurysm of the Internal Carotid Artery. Front. Neurol. 2021, 12, 739222. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  24. Hayashi, J.; Sekine, Y.; Toyama, S.; Uchida, T.; Watanabe, T. Endovascular repair for arterio-venous fistula treatment: A case report. Gen. Thorac. Cardiovasc. Surg. Cases 2023, 2, 82. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  25. Sinha, V.K.; Yaduvanshi, A.; Kataria, V.; Nair, M. Traumatic Common Carotid-Internal Jugular Arteriovenous Fistula Manifesting as Life-Threatening Epistaxis. JACC Case Rep. 2019, 1, 576–578. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  26. Nawrocki, T.; Harfouch, N.; Rahman, M.; Roh, S.A.; Singh, K.; Greenstein, J.; Hahn, B. A Case Report of Delayed Presentation of a Carotid-Jugular Fistula Caused by Blunt Injury from an Arrow. J. Emerg. Med. 2021, 61, e137–e140. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  27. Halenda, K.M.; Rahimi, S.Y.; Patton, J.J.; Thomas, D.A. Sixth Nerve Palsy Secondary to Traumatic Carotid-Jugular Fistula. Neuroophthalmology 2018, 44, 41–44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  28. Liu, X.; Fan, L.; Ying, C.; Cheng, Y.; Wang, M. Traumatic extracranial internal carotid-jugular fistula leading to serious injury: A case report in forensic assessment. Forensic Sci. Res. 2018, 5, 170–173. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  29. Drevets, P.; Tien, L.; Alslaim, H.S.; Holmes, K.; Agarwal, G. Protective Arteriovenous Fistula in Traumatic Common Carotid Transection. Vasc. Endovasc. Surg. 2022, 56, 775–778. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  30. Siletz, A.; Inaba, K. Diagnostic approach to penetrating neck trauma: What you need to know. J. Trauma Acute Care Surg. 2024, 97, 175–182. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  31. Payman, A.A.; Pecoraro, N.C.; Tsiang, J.T.; Souter, J.; Hand, R.; Bechara, C.F.; Serrone, J.C. Stenting for Traumatic Pseudoaneurysms of the Cervical Internal Carotid Artery: Case Report and Systematic Review. World Neurosurg. 2024, 184, e603–e612. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  32. Coelho, H.A.; Albernaz, L.C.S.; de Aguiar, L.S.; Filho, A.S.M.; Soares, M.W.S.; Barbi, H.; de Almeida, J.F.F.; Foratto, A.; Cantador, A.A.; Perales, S.R. Post-traumatic pseudoaneurysm of the common carotid artery associated with arteriovenous fistula to the internal jugular vein: A case report. Trauma Case Rep. 2025, 60, 101270. [Google Scholar] [CrossRef] [Scilit] [PubMed]
  33. Ahmed, E.; Mohammad, A.; Khalid, S.; Rabbani, S.S.; Haseen, M.A.; Khursheed, A. Traumatic common carotid artery-internal jugular vein fistula in an acute setting: A case report with review of literature. Ann. Vasc. Surg. Brief Rep. Innov. 2025, 5, 100377. [Google Scholar] [CrossRef] [Scilit]
Figure 1. Sagittal CTA of the left neck demonstrating focal contrast extravasation adjacent to the LCCA along the penetrating wound tract, consistent with traumatic arterial injury. Visible bleeding is indicated by a red arrow.
Diagnostics 16 02411 g001
Figure 2. CTA demonstrating a contrast-filled pseudoaneurysm (red arrow) arising from the LCCA, with adjacent post-traumatic hematoma.
Diagnostics 16 02411 g002
Figure 3. Selective DSA of the LCCA demonstrating a traumatic carotid–jugular AVF with early opacification of the LIJV and an associated LCCA pseudoaneurysm. The green arrow indicates the AVF, and the red arrow indicates the LIJV.
Diagnostics 16 02411 g003
Figure 4. Completion DSA after covered stent-graft implantation showing exclusion of the pseudoaneurysm and AVF, with preserved antegrade flow through the LCCA and carotid bifurcation. The implanted stent-graft is indicated by the red arrow.
Diagnostics 16 02411 g004
Table 1. Comparison of imaging techniques used in the assessment of suspected cervical arteriovenous fistula and pseudoaneurysm.
TechniqueMain AdvantagesMain LimitationsPotential Role in Suspected Cervical AVF/Pseudoaneurysm
Doppler ultrasonography (DUS)Bedside availability; no ionizing radiation; real-time assessment of flow and vessel wall abnormalities; may demonstrate turbulent flow, arterialized venous waveform, low-resistance arterial flow, a wall defect and pseudoaneurysm flow patterns [1,3,8].Operator-dependent; limited by pain, hematoma, dressings, subcutaneous air, metallic fragments, deeply located lesions and restricted acoustic windows.Useful adjunct for accessible lesions and follow-up; may define a wall defect, hematoma morphology, flow disturbance and extrinsic vessel compression, but may not fully characterize complex penetrating neck injury.
Contrast-enhanced ultrasonography (CEUS)No ionizing radiation; dynamic visualization of contrast within a vascular cavity; may improve detection of low-flow or equivocal vascular communication.Operator-dependent; limited field of view and acoustic access; lower availability; evidence in acute penetrating neck trauma is limited.Potential adjunct in selected patients or during follow-up when conventional DUS is inconclusive and cross-sectional imaging is undesirable.
Computed tomography angiography (CTA)Rapid and widely available; evaluates the wound trajectory, arterial and venous injuries, active extravasation, pseudoaneurysm, early venous opacification, hematoma, retained foreign bodies and associated skeletal or aerodigestive injuries [11,12,14,15,16,17].Ionizing radiation and iodinated contrast exposure; metal-related streak artifacts; primarily anatomical and less dynamic than catheter angiography.First-line cross-sectional imaging in hemodynamically stable penetrating neck trauma when vascular injury is suspected; provides an anatomical roadmap for management.
Magnetic resonance angiography (MRA)No ionizing radiation; excellent soft-tissue contrast; multiplanar assessment; may be useful in selected subacute or follow-up settings.Longer acquisition time; motion sensitivity; limited emergency availability; monitoring constraints; susceptibility artifacts and safety concerns in patients with retained metallic fragments.Usually not a first-line test in acute penetrating neck trauma; may be considered for selected delayed assessments or follow-up when feasible.
Digital subtraction angiography (DSA)High spatial and temporal resolution; dynamic demonstration of arteriovenous shunting, parent vessel involvement, collateral circulation and immediate treatment response; enables simultaneous endovascular treatment [5,9,10,18,19].Invasive; ionizing radiation; iodinated contrast exposure; access-site and catheter-related procedural risks.Used when CTA demonstrates or strongly suggests a treatable vascular lesion; confirms fistula hemodynamics, guides device deployment and verifies treatment success.
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content.