1. Introduction
Chronic obstructive pulmonary disease (COPD) and heart failure (HF) frequently coexist in older, multimorbid patients, and this overlap has important clinical consequences. Dyspnoea, exercise intolerance, and fatigue are nonspecific symptoms that may arise from either organ system, making diagnostic assessment and longitudinal follow-up more difficult. When both diseases are present, patients generally experience more hospitalizations, more complex treatment decisions, and a worse prognosis than those with either condition alone [
1,
2,
3].
The overlap between COPD and HF is not merely epidemiological. Both conditions are linked to smoking exposure, ageing, systemic inflammation, endothelial dysfunction, oxidative stress, and vascular disease, and each may amplify the clinical burden of the other [
4,
5,
6]. COPD may contribute to adverse cardiopulmonary interactions through hypoxia, pulmonary vascular changes, and impaired reserve, whereas HF can aggravate respiratory symptoms through congestion and reduced pulmonary compliance.
Management is therefore challenging. In routine practice, worsening symptoms may be attributed to the wrong organ system, delaying recognition of decompensation. Clinicians may also hesitate to intensify HF therapy when chronic lung disease is present, while respiratory disease severity is often incompletely characterized in cardiology-led settings [
1,
2,
3,
7].
Sodium-glucose cotransporter 2 inhibitors (SGLT2is) are now a cornerstone of guideline-directed medical therapy for HF, with evidence of benefit across reduced, mildly reduced, and preserved ejection fraction [
8,
9,
10,
11]. Beyond their established effects on HF hospitalization and cardiovascular outcomes, these agents may also modulate inflammatory pathways and influence respiratory outcomes, including COPD exacerbation risk [
12,
13,
14]. However, it remains uncertain whether SGLT2i initiation attenuates the adverse prognostic signal associated with coexisting COPD in real-world HF populations.
We therefore assessed whether a documented baseline diagnosis of COPD was associated with greater biomarker burden and worse 12-month outcomes after SGLT2i initiation in a real-world HF cohort.
2. Materials and Methods
2.1. Study Design and Setting
This prospective observational study was conducted at University Hospital Dubrava, Zagreb, Croatia, a tertiary HF referral centre. Consecutive patients were enrolled in the institutional HF registry between May 2022 and November 2024 after providing written informed consent. The study is reported in accordance with the Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) statement. The registry prospectively captured baseline demographics, comorbidities, laboratory variables, echocardiography, treatment data, and follow-up outcomes during routine clinical care.
Treatment decisions, including the choice of dapagliflozin or empagliflozin and subsequent HF titration, were left to the treating cardiologist in accordance with contemporary European Society of Cardiology (ESC) guidance [
8], local reimbursement criteria, and routine clinical practice. No protocol-specific treatment algorithm determined SGLT2i selection or later medication escalation.
2.2. Participants and Inclusion Criteria
Patients with HF were eligible regardless of aetiology (ischemic or non-ischemic) or clinical setting (new-onset, acute-on-chronic, inpatient, or outpatient), provided that SGLT2i therapy was initiated during the index evaluation.
HF diagnosis was established according to contemporary ESC criteria [
8]. Accordingly, participants were required to have compatible symptoms and/or signs of HF, echocardiographic evidence of structural and/or functional cardiac abnormality, and elevated NT-proBNP at baseline (>300 pg/mL in patients without ongoing atrial fibrillation or flutter and >600 pg/mL in patients with ongoing atrial fibrillation or flutter). Left ventricular ejection fraction (LVEF) was assessed by the modified Simpson method by two independent echocardiographers. HF phenotypes were classified according to ESC criteria as heart failure with reduced ejection fraction (HFrEF; LVEF ≤ 40%), heart failure with mildly reduced ejection fraction (HFmrEF; LVEF 41–49%), and heart failure with preserved ejection fraction (HFpEF; LVEF ≥ 50%).
Patients in whom SGLT2i therapy was not initiated were not included. Patients in whom SGLT2i therapy was later discontinued remained in the registry and were followed according to protocol. All baseline clinical, laboratory, and echocardiographic data were obtained before SGLT2i initiation.
2.3. Data Collection, COPD Ascertainment, and Outcome Definitions
We collected sociodemographic characteristics, body mass index, New York Heart Association (NYHA) class, smoking history, comorbidities, laboratory values, echocardiographic variables, HF medications, hospitalizations, and mortality. Data were recorded at baseline and at the 6-month and 12-month follow-up visits within the prospective registry and were supplemented by a review of the electronic hospital record. Comorbidity burden was therefore represented by individual conditions rather than by a composite score such as the Charlson Comorbidity Index.
Participants were grouped according to baseline COPD status. In the main comparative cohort, COPD was defined by a documented pre-existing clinical diagnosis at the index visit; post-bronchodilator spirometry was not mandated by the study protocol. In accordance with the Global Initiative for Chronic Obstructive Lung Disease (GOLD), the reference standard for COPD diagnosis is post-bronchodilator spirometry demonstrating persistent airflow obstruction (forced expiratory volume in 1 s/forced vital capacity [FEV1/FVC] < 0.70) [
15]. Smoking exposure in the registry was recorded as current, former, or never smoking and was collapsed a priori into a binary smoking-history variable for subgroup analyses (ever-smoker: current or former smoker; never-smoker: no smoking history), which is the stratification used in
Figure 1 and
Figure 2. To further characterize respiratory status within the same 122-patient analytical COPD cohort, we performed a structured descriptive review of available specialist pulmonology records corresponding to those patients. When available, these records provided information on spirometry, GOLD stage/group, inhaled therapy, and exacerbation history; however, because this additional respiratory documentation remained incomplete and not fully standardized, it was reserved for descriptive reporting and was not used to redefine COPD status or enter the primary Cox models.
The primary outcome was the 12-month time-to-first composite of all-cause death or unplanned hospitalization for acute decompensated HF. Secondary outcomes were all-cause death and HF hospitalization, analysed separately. HF hospitalization was defined as an unscheduled hospital admission primarily attributed to acute decompensated HF, accompanied by worsening symptoms and/or signs considered by the treating team to reflect HF and requiring inpatient intensification of HF-directed therapy. When admissions in patients with COPD raised overlapping cardiorespiratory diagnostic questions, the primary discharge diagnosis and inpatient treatment course recorded in the electronic hospital record were used for event classification. Outcomes were ascertained through telephone interviews, regular outpatient follow-up, and review of electronic hospital records. For time-to-event analyses, follow-up began at SGLT2i initiation and was administratively censored at 12 months. Serial biomarker analyses used all available repeated measurements at 6 and/or 12 months.
2.4. Statistical Analysis
Continuous variables are presented as medians and interquartile ranges and categorical variables as counts and proportions. Distribution normality was screened with the Kolmogorov–Smirnov test, and markedly skewed variables such as NT-proBNP were log-transformed for regression analyses. Between-group comparisons at baseline or at single follow-up timepoints used the Mann–Whitney U test for continuous variables and the chi-square test for categorical variables. Associations with outcomes were evaluated using univariable and multivariable Cox proportional hazards regression analyses. For the primary composite endpoint, time-to-event analyses used the first qualifying event; accordingly, a patient hospitalized for HF and dying later contributed the date of the first HF hospitalization to the composite endpoint analysis. In the separate all-cause mortality analysis, patients were censored at 12 months if they were alive. In the separate HF-hospitalization analysis, patients were censored at death or at 12 months if no qualifying HF admission had occurred.
Covariates for multivariable modelling were prespecified on the basis of clinical relevance and data completeness and included sex, age, history of stroke, atrial fibrillation or flutter, COPD, peripheral artery disease, prior hospitalization for acute coronary syndrome, NYHA class III/IV, body mass index, high-density lipoprotein cholesterol, LVEF, estimated glomerular filtration rate, CRP, glycated haemoglobin, and log NT-proBNP. Chloride was examined only in a sensitivity model because of greater missingness. The primary Cox models were fitted in the full comparative cohort, whereas subset-level respiratory variables were reserved for descriptive and exploratory analyses. Because serial biomarker availability declined during follow-up, the primary longitudinal presentation retained available-case between-group comparisons at each time point. Additional within-patient longitudinal analyses were undertaken in patients with repeated biomarker measurements available from pulmonology follow-up. Baseline-to-6-month and baseline-to-12-month changes in NT-proBNP and CRP were assessed with Wilcoxon signed-rank tests using all available pairs. In patients with complete baseline, 6-month, and 12-month biomarker data, the Friedman test was used to explore an overall time effect across the three visits. These longitudinal analyses were exploratory and complemented, rather than replaced, the prespecified cohort-level comparisons. Missing serial values were not imputed; each analysis used the maximum number of complete cases available for the relevant variable and time point. Multivariable models were built with a forward conditional approach. A two-sided p-value < 0.05 was considered statistically significant. Primary analyses were performed in IBM SPSS Statistics version 30.0 (IBM Corp., Armonk, NY, USA).
2.5. Ethics
This study was approved by the Ethics Committee of University Hospital Dubrava (Klinička bolnica Dubrava), Zagreb, Croatia (approval code: 2022/1403-01; date of approval: 14 March 2022). Written informed consent was obtained from all participants in accordance with the approved protocol.
3. Results
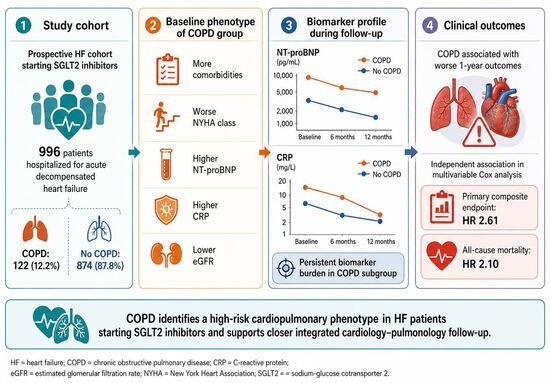
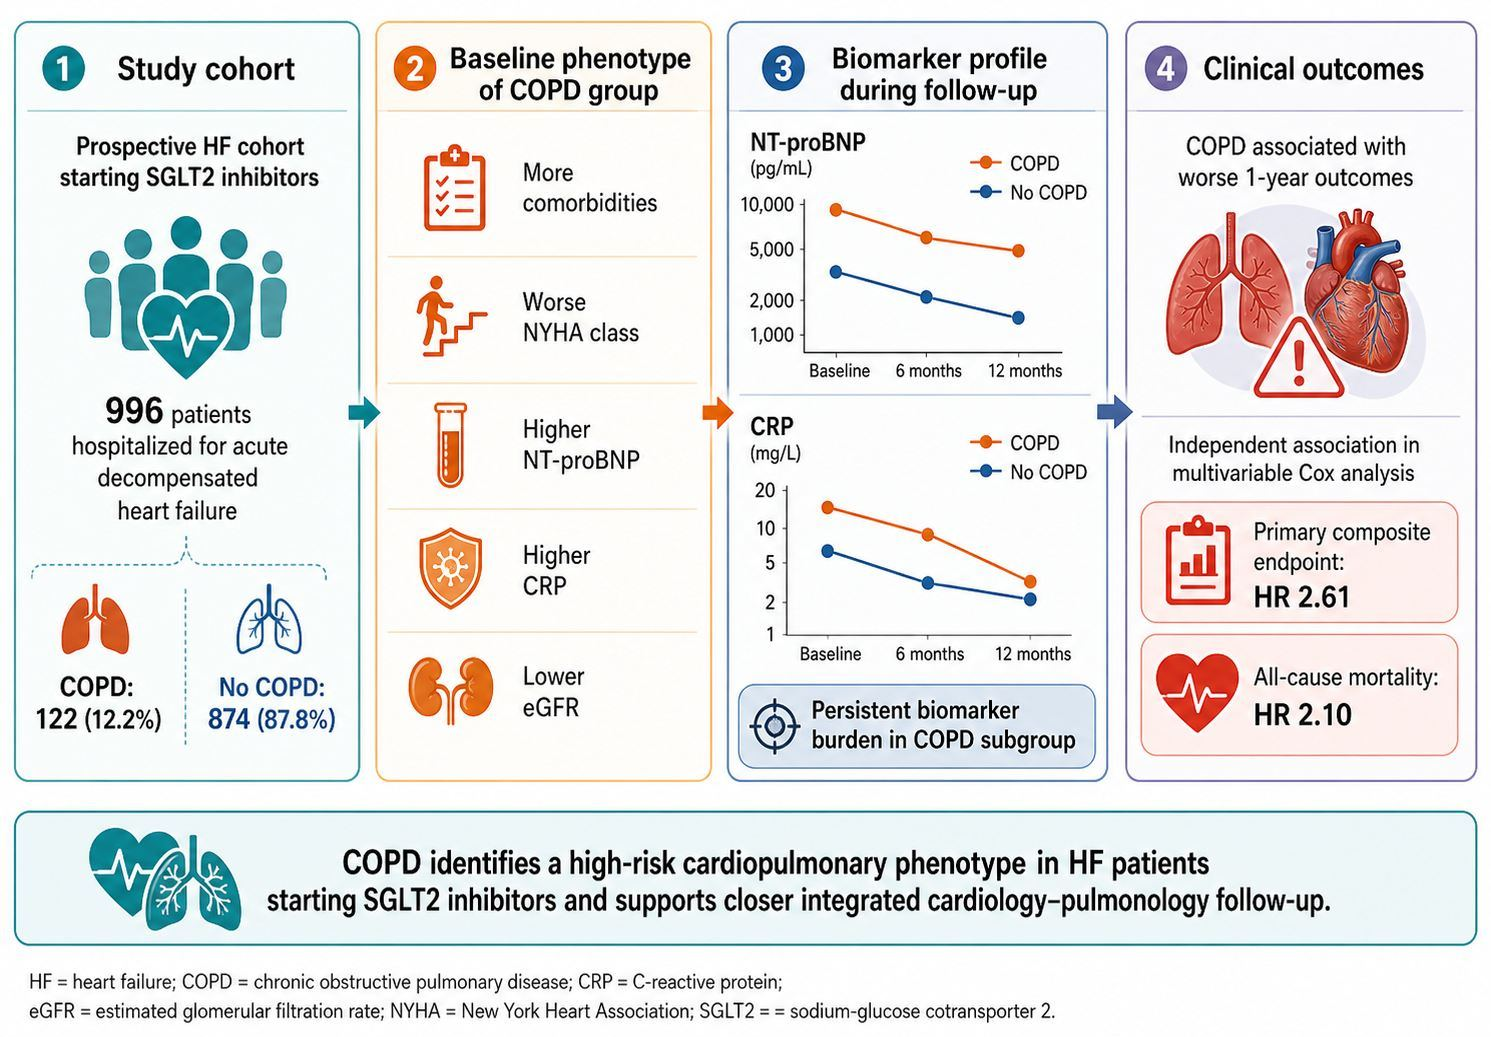
A total of 996 patients were included in the analysis. The population was predominantly male (67.3%), with a median age of 70 (62–76) years. In total, 122 patients (12.2%) had an established diagnosis of COPD. HFrEF was the prevailing phenotype in both groups (56.6% in COPD vs. 60.9% without COPD), and the median LVEF was similar.
Compared with patients without COPD, those with COPD had a higher burden of comorbidities, including hypertension, diabetes, and peripheral artery disease. They more often presented with NYHA class III or IV symptoms and were more likely to have a smoking history. Baseline NT-proBNP and CRP levels were higher, and eGFR was lower in the COPD group. Core baseline HF pharmacotherapy was otherwise broadly similar between groups, including beta-blockers, angiotensin-converting enzyme inhibitors or angiotensin receptor blockers (ACEis/ARBs), angiotensin receptor neprilysin inhibitors (ARNIs), and mineralocorticoid receptor antagonists (MRAs), although dapagliflozin was used more often in patients with COPD (
Table 1).
To further characterize respiratory status within the same analytical COPD cohort, we performed a descriptive review of available specialist pulmonology records corresponding to the 122 registry-defined COPD patients. Spirometry was available in 99/122 (81.1%), GOLD stage/group classification in 57/122 (46.7%), and documented inhaler data in 119/122 (97.5%). Among patients with documented inhaler data, 113/119 (95.0%) were receiving at least one inhaled therapy at baseline: LABA 78/119 (65.5%), ICS 58/119 (48.7%), LAMA 57/119 (47.9%), SAMA 23/119 (19.3%), SABA 14/119 (11.8%), nebulized SABA/SAMA 8/119 (6.7%), and LABA/LAMA/ICS triple therapy 26/119 (21.8%). At least one recorded exacerbation was documented in 53/122 (43.4%). These respiratory variables were descriptive only and were not used in the primary comparative models.
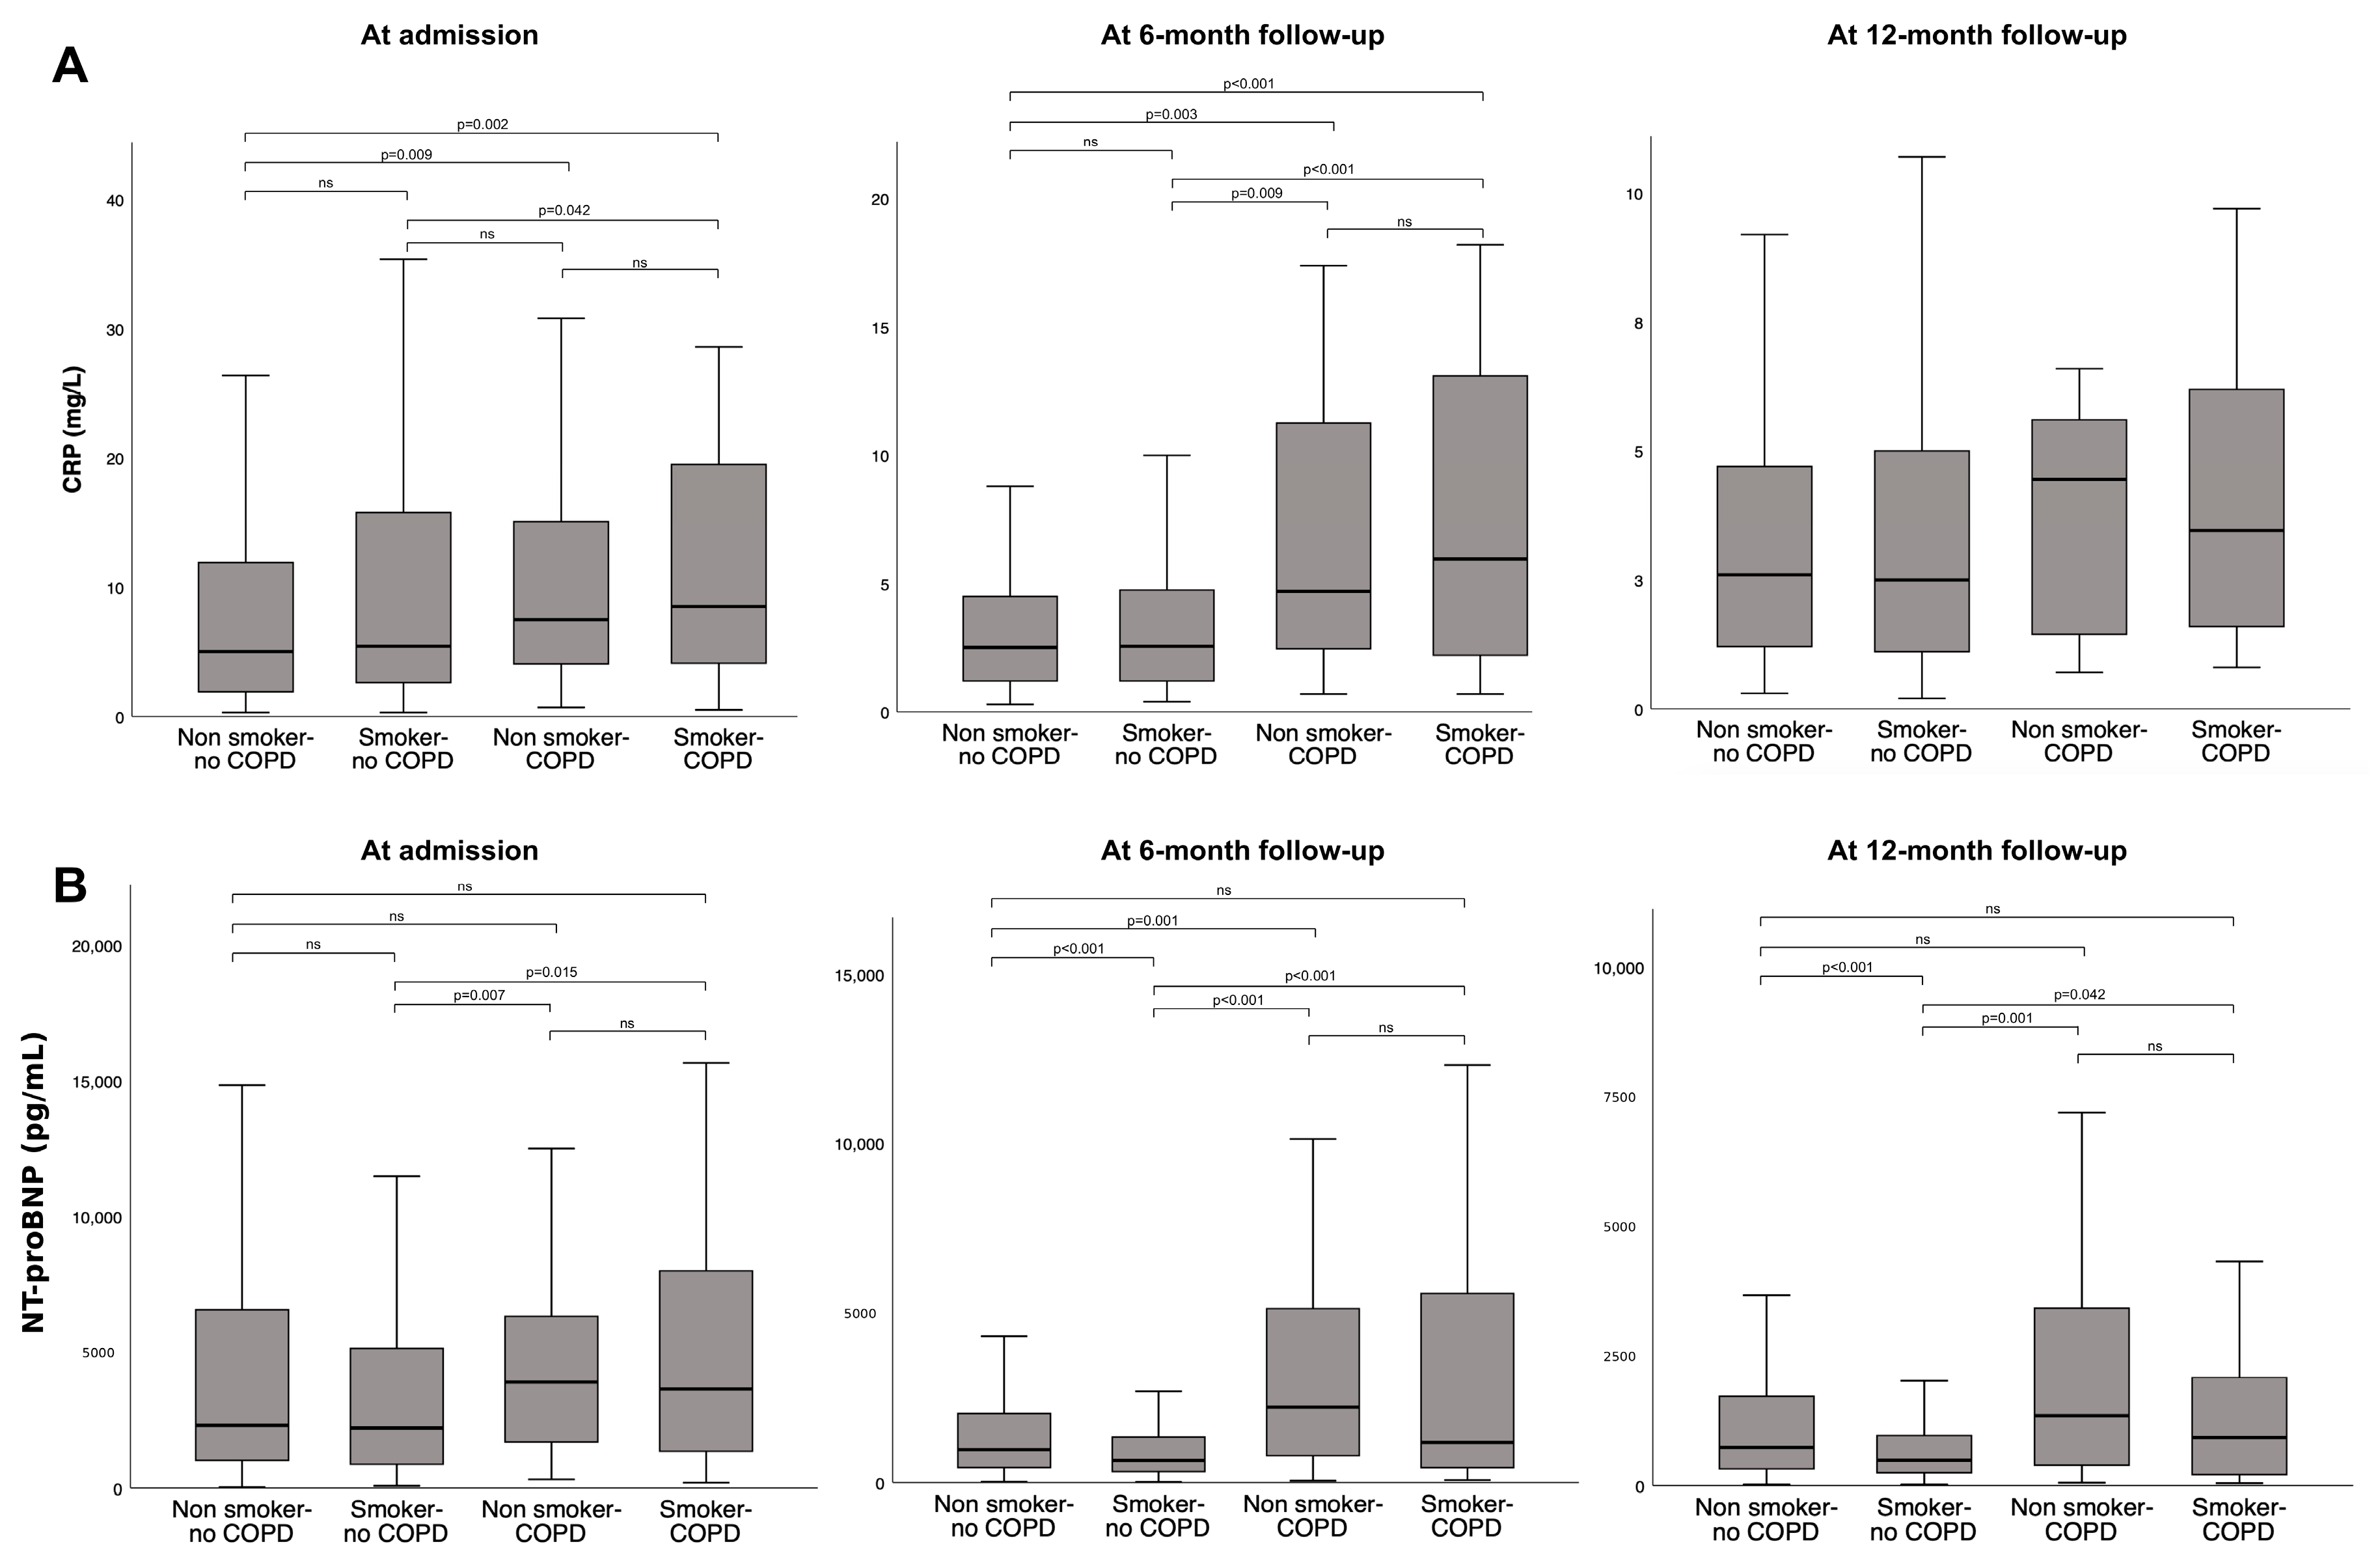
In patients with COPD, NT-proBNP remained higher at both the 6-month and 12-month follow-up assessments, whereas CRP remained higher at 6 months but not at 12 months (
Table 2). Four-way stratification according to smoking history, defined as ever-smoker (current or former smoker) versus never-smoker (no smoking history), is presented in
Figure 1.
In exploratory within-patient longitudinal analyses, NT-proBNP declined significantly from baseline to 6 months (paired
n = 98; median 3882 vs. 1459 pg/mL; Wilcoxon
p < 0.001) and from baseline to 12 months (paired
n = 72; median 3561 vs. 1056.5 pg/mL;
p < 0.001). Among the 70 patients with complete measurements at all three time points, the Friedman test likewise supported an overall time effect for NT-proBNP (
p < 0.001). By contrast, paired CRP values trended downward but did not reach significance in the non-parametric paired analyses (baseline vs. 6 months:
n = 49,
p = 0.096; baseline vs. 12 months:
n = 31,
p = 0.112), and the Friedman test was likewise non-significant in the 21 patients with all three measurements (
p = 0.156). These exploratory analyses complemented, rather than replaced, the prespecified cohort-level between-group comparisons reported in
Table 2.
Formal longitudinal comparisons of HF-treatment intensification or inhaled therapy escalation were not feasible because follow-up treatment changes were not captured in a sufficiently standardized manner across the analytical COPD cohort.
The primary composite endpoint and each of its individual components occurred more frequently in patients with COPD (
Table 1).
Several Cox regression models were fitted using a forward conditional approach. In the multivariable model including 15 variables (sex, age, history of stroke, atrial fibrillation or flutter [AFib], COPD, peripheral artery disease [PAD], prior hospitalization for acute coronary syndrome [ACS], NYHA class III/IV, body mass index, high-density lipoprotein cholesterol, LVEF, estimated glomerular filtration rate, CRP, glycated haemoglobin [HbA1c], and log NT-proBNP), all-cause death was independently associated with age (HR 1.063; 95% CI 1.035–1.093; p < 0.001), high-density lipoprotein cholesterol (HR 0.241; 95% CI 0.106–0.546; p < 0.001), history of stroke (HR 2.098; 95% CI 1.177–3.739; p = 0.012), log NT-proBNP (HR 1.591; 95% CI 1.281–1.975; p < 0.001), and COPD (HR 2.097; 95% CI 1.246–3.532; p = 0.005).
In the corresponding model for the primary composite endpoint, age (HR 1.042; 95% CI 1.020–1.064;
p < 0.001), HDL cholesterol (HR 0.270; 95% CI 0.139–0.527;
p < 0.001), history of stroke (HR 2.531; 95% CI 1.580–4.054;
p < 0.001), log NT-proBNP (HR 1.676; 95% CI 1.402–2.004;
p < 0.001), and COPD (HR 2.610; 95% CI 1.707–3.991;
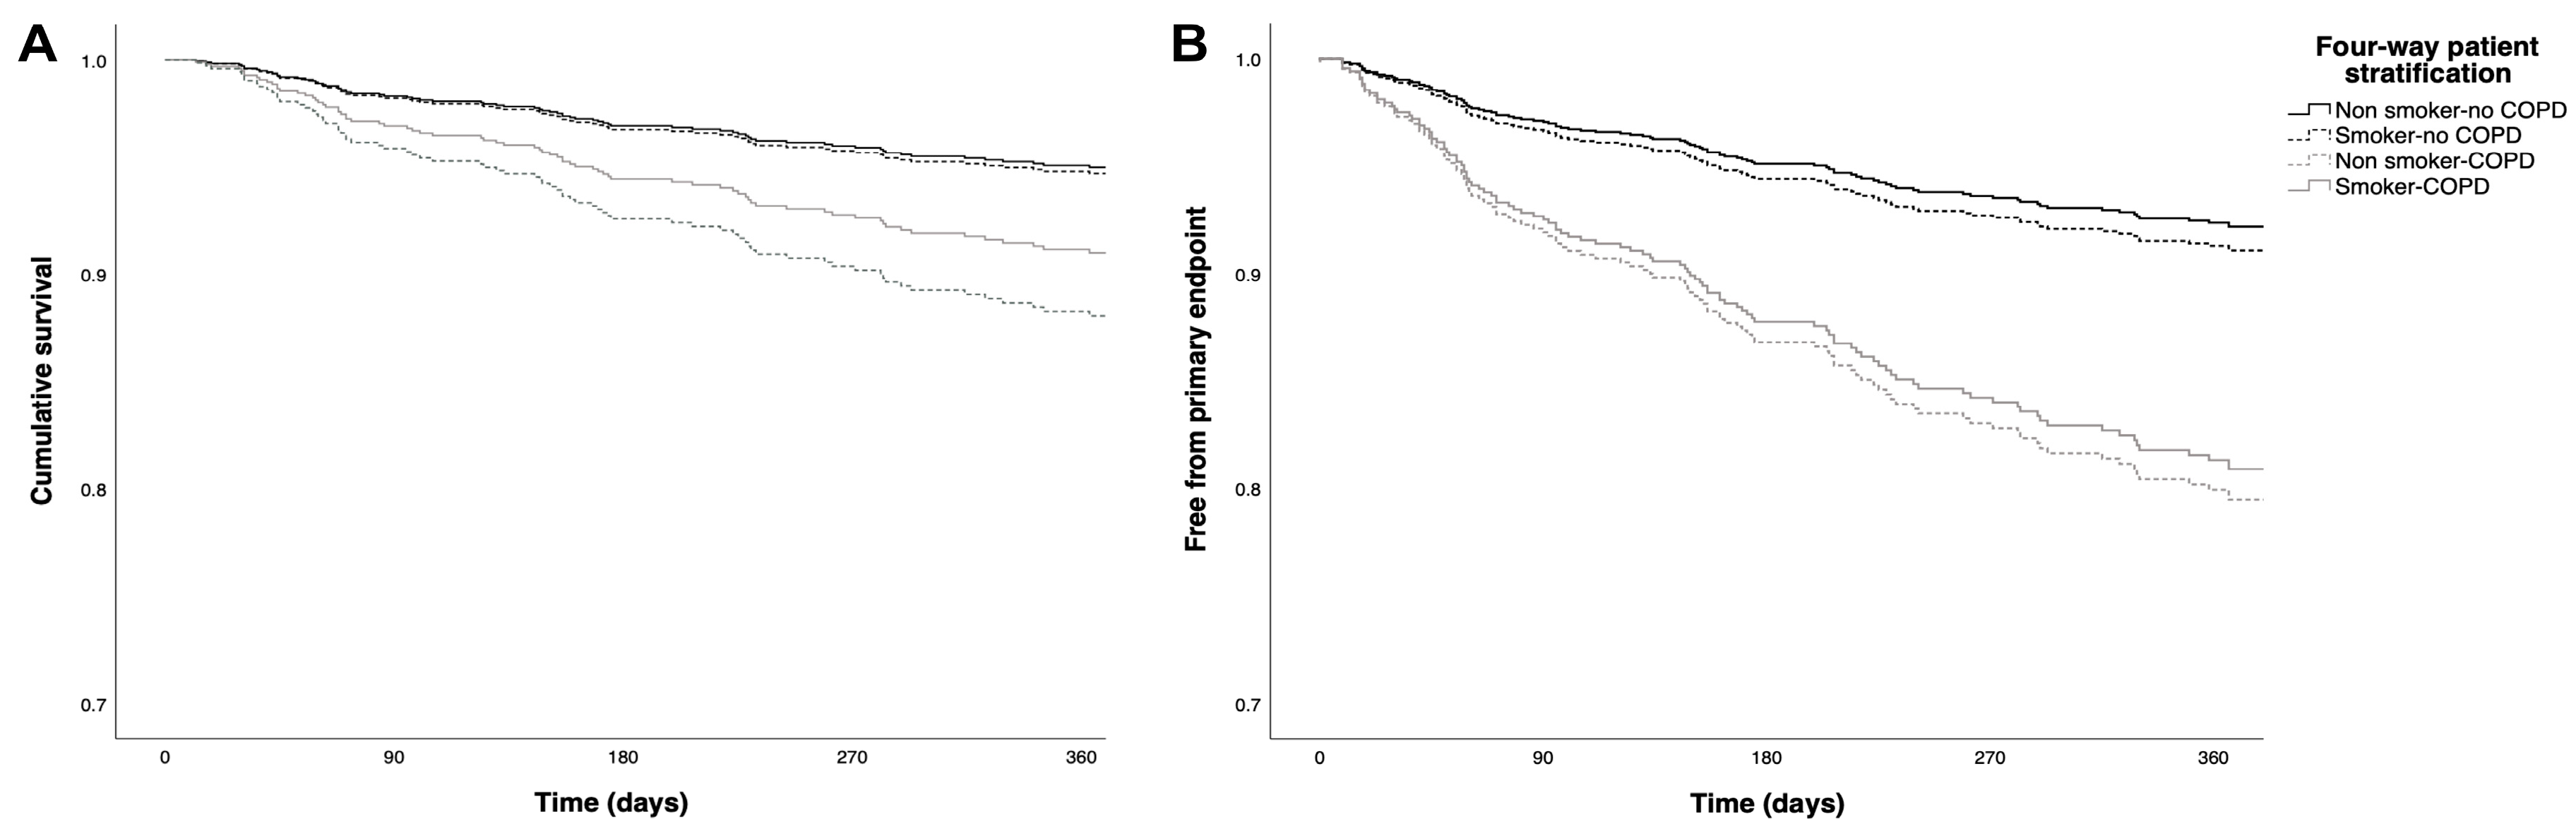
p < 0.001) remained independent predictors. Importantly, the association between COPD and outcome persisted despite adjustment for LVEF and major comorbidities. Similar results were observed with four-way stratification of the study population. Survival curves are shown in
Figure 2.
Chloride was excluded from the primary models because of a higher proportion of missing data (30.8%). When chloride was forced into the model as a sixteenth covariate, reducing the analyzable cohort to 61.2% of all cases, COPD was no longer an independent predictor of all-cause death but remained a predictor of the primary outcome. This exploratory finding should be interpreted cautiously, given the degree of missingness.
4. Discussion
In this prospective observational cohort of 996 patients with heart failure (HF) at the time of sodium-glucose cotransporter 2 inhibitor (SGLT2i) initiation, coexisting chronic obstructive pulmonary disease (COPD) identified a clinically distinct high-risk subgroup. Patients with COPD had a heavier comorbidity burden, more advanced symptoms, higher CRP at baseline and 6 months, persistently higher NT-proBNP throughout follow-up, and significantly worse 1-year outcomes. Importantly, COPD remained independently associated with all-cause death and with the composite endpoint after adjustment for age, LVEF, NT-proBNP, renal function, and major comorbidities.
Our findings are consistent with previous work showing that HF-COPD overlap is associated with worse prognosis, more frequent hospital use, and more complicated day-to-day management [
1,
2,
3,
7,
16,
17,
18]. The present study extends this literature by focusing on a contemporary real-world HF cohort at a standardized treatment milestone, namely cohort entry at SGLT2i initiation. This design should be interpreted as an observational context rather than as an interventional evaluation of SGLT2i efficacy.
The role of SGLT2i in the present study is therefore contextual rather than causal. The use of SGLT2i therapy defined cohort entry and reflects contemporary guideline-directed HF care [
8,
9,
10,
11]. Although experimental and clinical studies have suggested anti-inflammatory effects and possible respiratory benefits [
12,
13,
14], our study was not designed to determine whether SGLT2i therapy modifies respiratory status or outcomes according to COPD status. Rather, the data indicate that documented COPD continued to identify a higher-risk phenotype within a treatment pathway that included SGLT2i.
These observations highlight the importance of integrated cardiology–pulmonology care. In patients with coexisting HF and COPD, dyspnoea, cough, wheeze, fatigue, exercise intolerance, and biomarker abnormalities rarely arise from a single isolated process. Persistent symptoms after apparent HF stabilization may justify respiratory reassessment, whereas worsening respiratory complaints in COPD should not automatically be attributed to lung disease alone. A shared follow-up framework that integrates natriuretic peptides, congestion assessment, echocardiography, oxygenation, inhaler adherence, exacerbation history, and pulmonary function testing, when clinically feasible, may improve diagnostic precision.
Additional respiratory characterization within the analytical COPD cohort suggests that these patients carried a clinically meaningful pulmonary disease burden rather than representing a loosely defined comorbidity subgroup. The high baseline use of inhaled therapy and the frequent history of exacerbations point to established chronic airway disease, whereas the incomplete availability of spirometry and GOLD classification reflects the limitations of respiratory phenotyping in routine HF care. This combination is clinically relevant because it can complicate the interpretation of dyspnoea and decompensation episodes and supports a more integrated cardiology-pulmonology approach in patients with overlapping HF and COPD.
The COPD group also had a higher burden of hypertension, diabetes, peripheral artery disease, and smoking history. Smoking almost certainly contributes to part of this excess multimorbidity burden, particularly with respect to vascular disease, but it is unlikely to be the sole explanation. COPD remained independently associated with outcome after multivariable adjustment, and in the four-way stratification, the most adverse pattern clustered with established COPD rather than with smoking history alone. This supports the concept that clinically manifest COPD identifies a broader cardiopulmonary vulnerability rather than only a marker of tobacco exposure.
It is also notable that the worse outcomes in COPD were not obviously explained by less intensive baseline HF pharmacotherapy. Core baseline guideline-directed medical therapy (GDMT) components, including beta-blockers, ACEi or ARB, ARNI, MRA, and SGLT2i initiation, were broadly similar between groups, which is reassuring because therapeutic hesitation still exists in patients with concomitant lung disease. However, longitudinal comparative titration data were not captured in a sufficiently standardized format across the cohort. Accordingly, these results should not be interpreted as evidence of differential treatment intensification during follow-up.
The biomarker trajectory in our cohort offers additional descriptive insight. Persistently higher NT-proBNP at 6 and 12 months suggests sustained haemodynamic stress or incomplete risk normalization during follow-up, while higher CRP at baseline and 6 months supports a contribution of ongoing systemic inflammation [
19]. The exploratory longitudinal analyses suggest that the largest NT-proBNP improvement occurred between baseline and 6 months, with a smaller subsequent change thereafter; clinically, this still identifies a subgroup in whom biomarker normalization remained incomplete over time. Lower chloride in the COPD group may reflect a more congested, more diuretic-exposed, or more metabolically fragile phenotype, although this observation should be considered exploratory because of missing data. Troponin was not systematically available in the registry and therefore could not be used to refine myocardial injury risk in the present analysis.
The distribution of the HF phenotype also deserves comment. HFrEF predominated in both groups, median LVEF was similar, and COPD remained independently associated with outcome even after LVEF adjustment. This suggests that the observed excess risk was not explained simply by a different LVEF profile. Nevertheless, the registry was not designed for a detailed phenotype-specific comparison across HFrEF, HFmrEF, and HFpEF, and those subgroup analyses should be addressed in future studies with more granular phenotyping.
Several clinically relevant mediators could not be explored in detail. Even after restricting the descriptive respiratory review to the same 122 analytical COPD patients, GOLD severity classification was available in fewer than half of the patients, and asthma overlap could not be reliably separated in all cases, precluding formal severity-adjusted analyses. We also lacked systematic data on pulmonary hypertension or right-sided haemodynamics, troponin, bronchiectasis, and prospectively adjudicated severe aortic stenosis.
Taken together, our findings suggest that documented COPD identifies a clinically recognizable high-risk cardiopulmonary phenotype among patients with HF starting SGLT2i therapy. In this population, recurrent dyspnoea, biomarker elevation, and interval clinical deterioration warrant careful joint cardiac and respiratory interpretation. These observational data support a closer integrated assessment, but they should not be interpreted as evidence of a treatment effect.
Limitations
This study has several limitations. First, its observational single-centre design precludes causal inference and limits generalizability. Second, COPD status in the main comparative cohort was derived from documented medical history rather than protocolized post-bronchodilator spirometry. Although we restricted the additional respiratory review to the same 122 analytical COPD patients, spirometric confirmation and severity phenotyping remained incomplete (spirometry available in 99/122; GOLD classification in 57/122), and comparable pulmonary variables were not available for the non-COPD controls. Third, outcome classification relied on real-world clinical records without central blinded adjudication. Because acute exacerbations of COPD or respiratory infections may mimic or coexist with HF decompensation, some degree of event misclassification cannot be fully excluded despite the use of the primary discharge diagnosis and inpatient treatment course to classify HF hospitalizations. Fourth, serial biomarker measurements declined over time and were not complete across all visits, so the paired Wilcoxon and Friedman analyses should be interpreted as exploratory longitudinal assessments rather than definitive longitudinal modelling across the whole cohort. Fifth, longitudinal titration of HF therapy and escalation of inhaled therapy were not captured in a sufficiently standardized format for formal comparative analysis. Sixth, several potentially relevant variables could not be fully addressed: asthma overlap could not be reliably separated in all cases, while pulmonary hypertension or right-sided haemodynamics, troponin, bronchiectasis, and systematically adjudicated severe aortic stenosis were not uniformly recorded. Finally, the cohort was derived from a tertiary HF centre and was predominantly composed of patients with HFrEF, which may limit applicability to broader HF populations and to phenotype-specific inference.




 ,