Survival Outcomes of BCG Only, BCG Plus EMDA-MMC or Upfront Radical Cystectomy in High-Risk Non-Muscle Invasive Bladder Cancers (NMIBCs): A Multicentre, International, Collaborative Study from Tertiary Referral Institutions
by
 , , , , , , , , , , add
Show full author list
Francesco Del Giudice
1,2,3,*,† ,
Valerio Santarelli
1,†, 
Amir Khan
4,
Mohamed Gad
3, 
Katarina Spurna
3,
Syed Ghazi Ali Kirmani
3,
Noor Huda Bhatti
3,
Rajesh Nair
3,
Kathryn Chatterton
3,
Suzanne Amery
3,
Elsie Mensah
3,
Benjamin Challacombe
3,
Youssef Ibrahim
3,
Felice Crocetto
5,
Giuseppe Basile
6,
Roberta Corvino
1,
Eleonora Razeto
1,
Matilde Verde
1,
Vincenzo Asero
1,
Ettore De Berardinis
1,
Giulio Garaffa
7,
Jan Łaszkiewicz
8,
Aleksander Ślusarczyk
9,
Francesco Claps
10,
Benjamin I. Chung
2,
Ramesh Thuraraja
3,
Timothy O’Brien
3,
Muhammad Shamim Khan
3,‡ and
Yasmin Abu-Ghanem
3,‡add
Show full author list
1
Department of Maternal-Infant and Urological Sciences, “Sapienza” University of Rome, Umberto I Hospital, 00185 Rome, Italy
2
Department of Urology, Stanford University School of Medicine, Stanford, Palo Alto, CA 94305, USA
3
Guy’s and St. Thomas’ NHS Foundation Trust, Guy’s Hospital, London SE1 9RT, UK
4
Division of Urology, Department of Surgery, University of Maryland, Baltimore, MD 21201, USA
5
Department of Neurosciences, Reproductive Sciences and Odontostomatology, University of Naples “Federico II”, 80131 Naples, Italy
6
Department of Urology, IRCCS Ospedale San Raffaele, Vita-Salute San Raffaele University, 20132 Milan, Italy
7
The Institute of Urology, University College London Hospitals, London NW1 2BU, UK
8
Department of Minimally Invasive and Robotic Urology, University Center of Excellence in Urology, Wroclaw Medical University, 50-556 Wroclaw, Poland
9
Department of General, Oncological and Functional Urology, Medical University of Warsaw, 02-091 Warsaw, Poland
10
Urological Clinic, Department of Medicine, Surgery and Health Sciences, University of Trieste, 34149 Trieste, Italy
*
Author to whom correspondence should be addressed.
†
These authors contributed equally to this work.
‡
These authors contributed equally to this work.
Cancers 2026, 18(3), 500; https://doi.org/10.3390/cancers18030500
Submission received: 19 December 2025
/
Revised: 27 January 2026
/
Accepted: 29 January 2026
/
Published: 3 February 2026
(This article belongs to the Special Issue Diagnosis and Therapy in Urothelial Cancer)
Simple Summary
In patients with high- and very high-risk Non-muscle-invasive Bladder Cancer, the risk of recurrence and progression remains high despite standard therapies. This multicentre study compared three adjuvant treatment strategies: BCG, BCG combined with electromotive administration of mitomycin C, and upfront radical cystectomy. The results showed no significant differences in survival outcomes among the treatment approaches. Instead, patient- and tumour-related factors, such as tumour stage, presence of concomitant carcinoma in situ, and repeat transurethral resection, had a greater impact on clinical outcomes. These findings suggest that treatment decisions should be individualized based on disease characteristics and patients’ preferences balanced with oncologic risk and clinical judgement.
Abstract
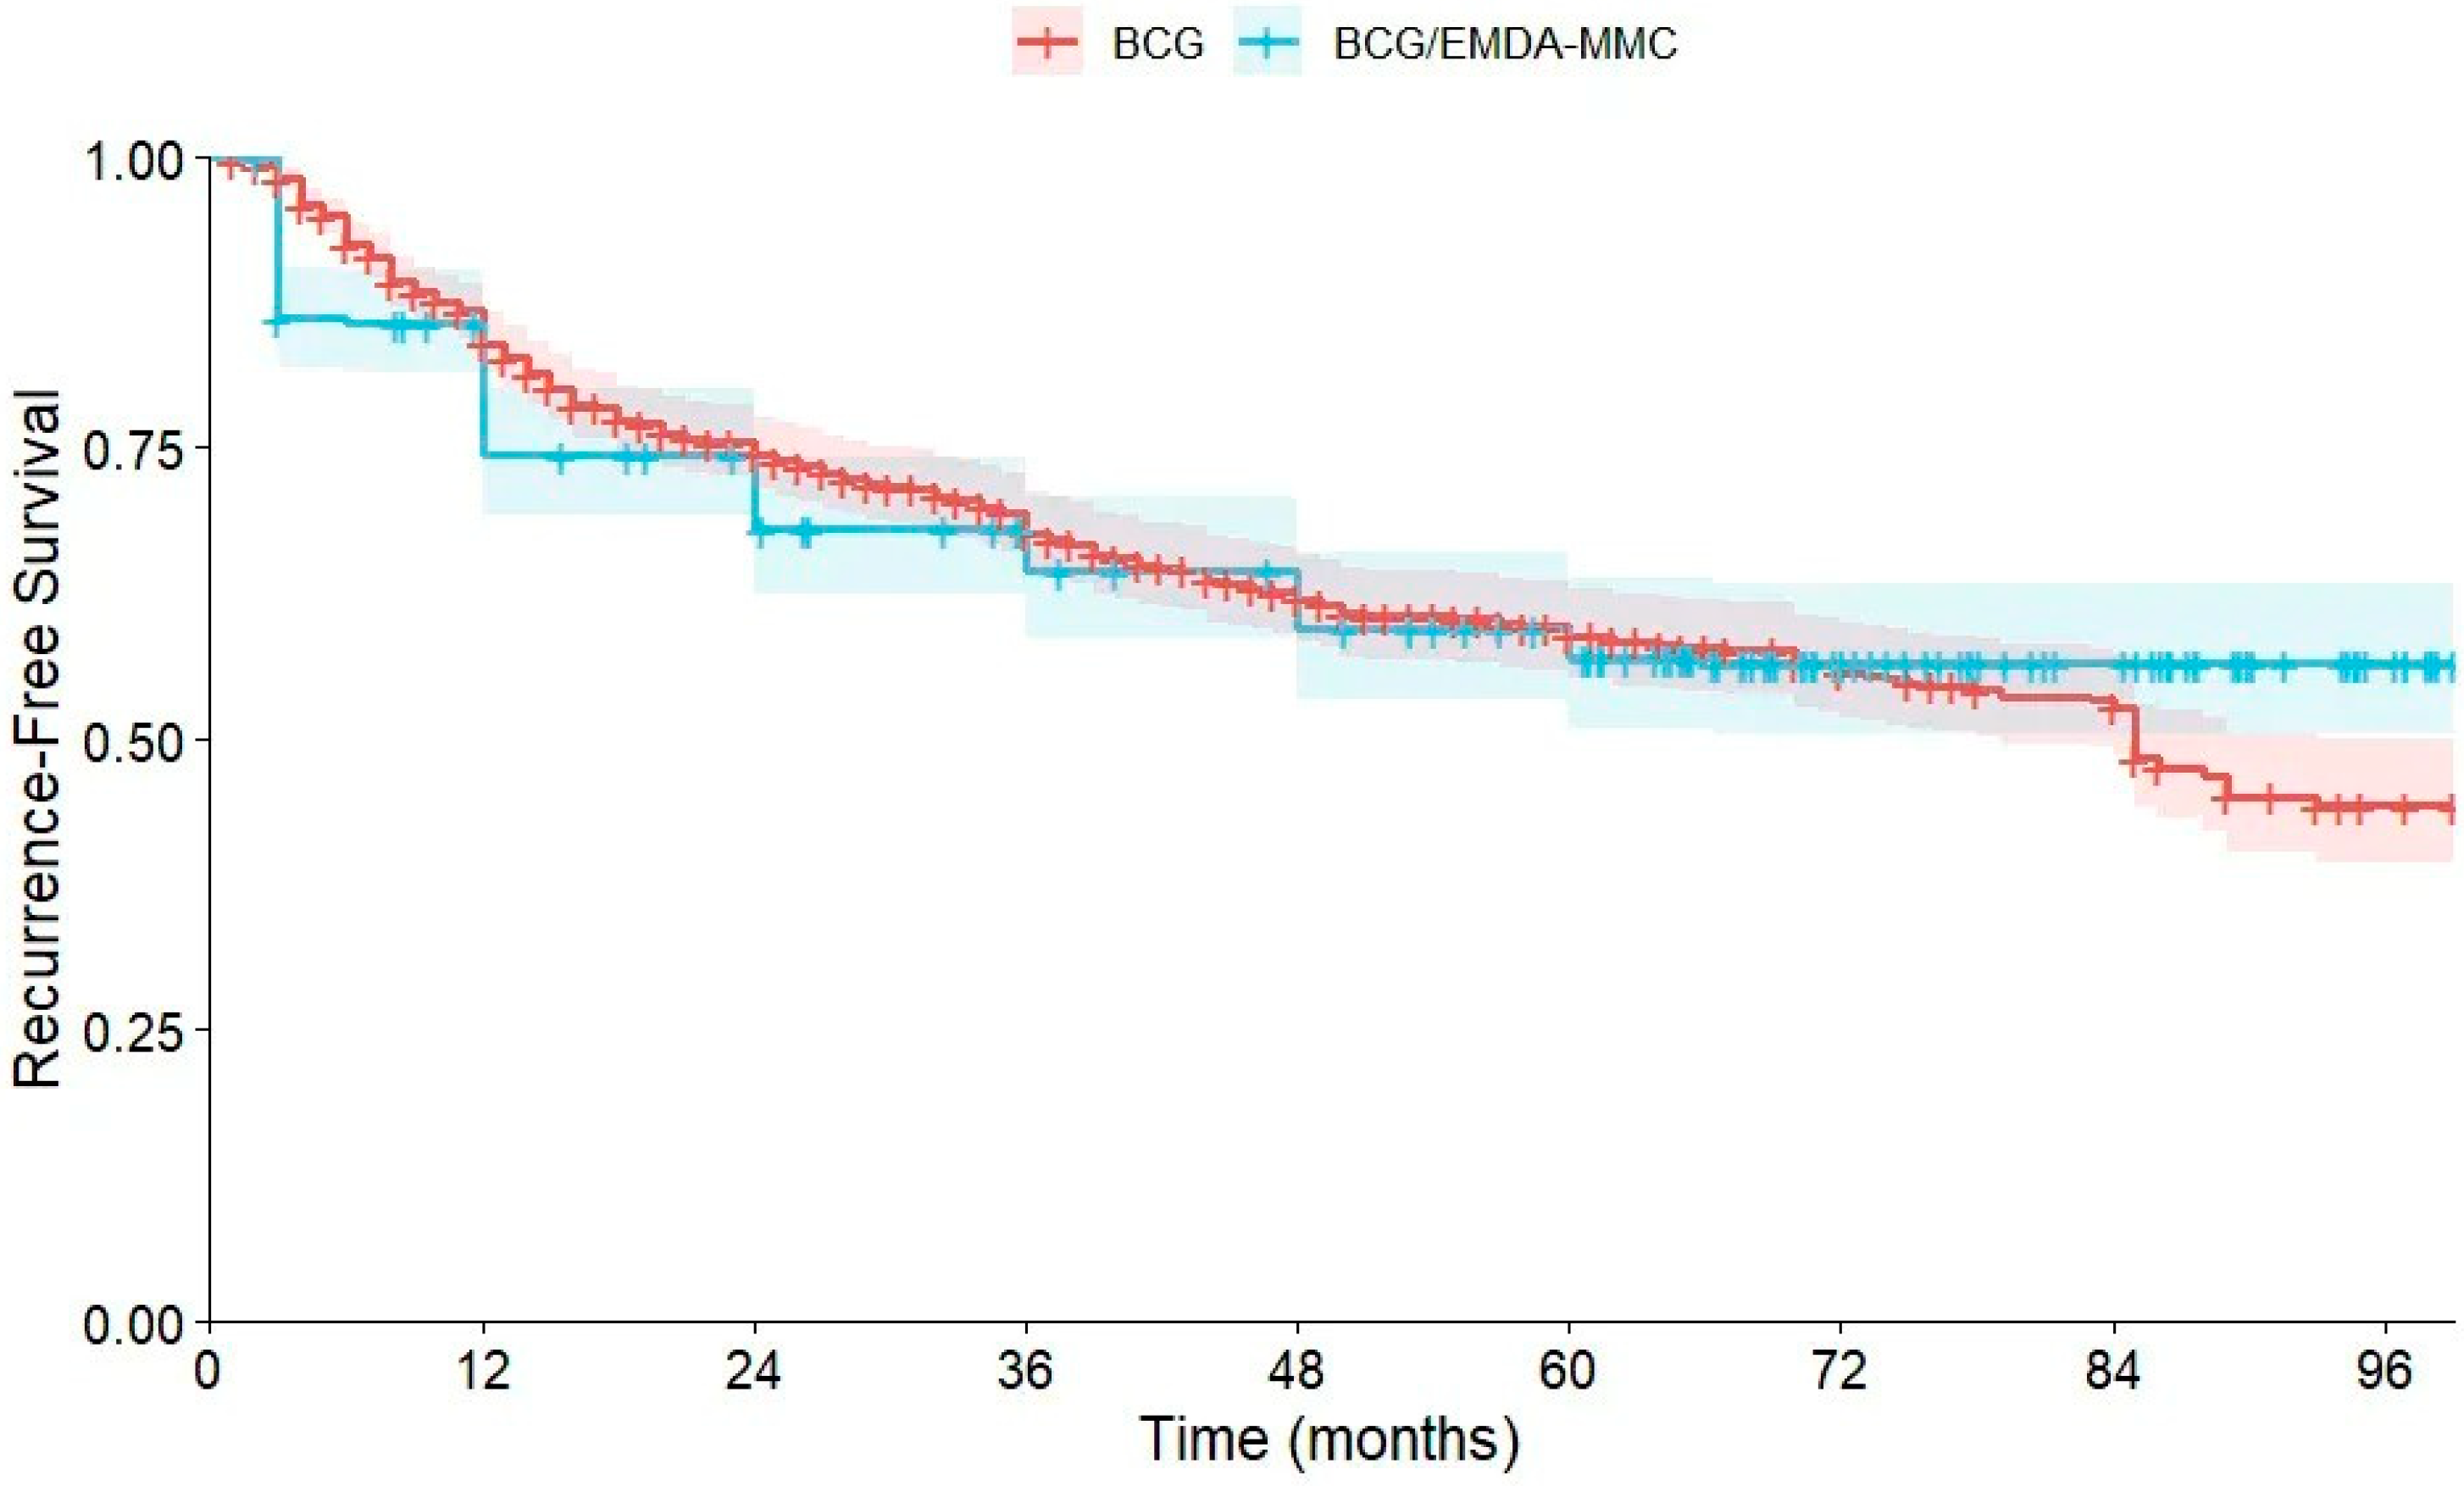
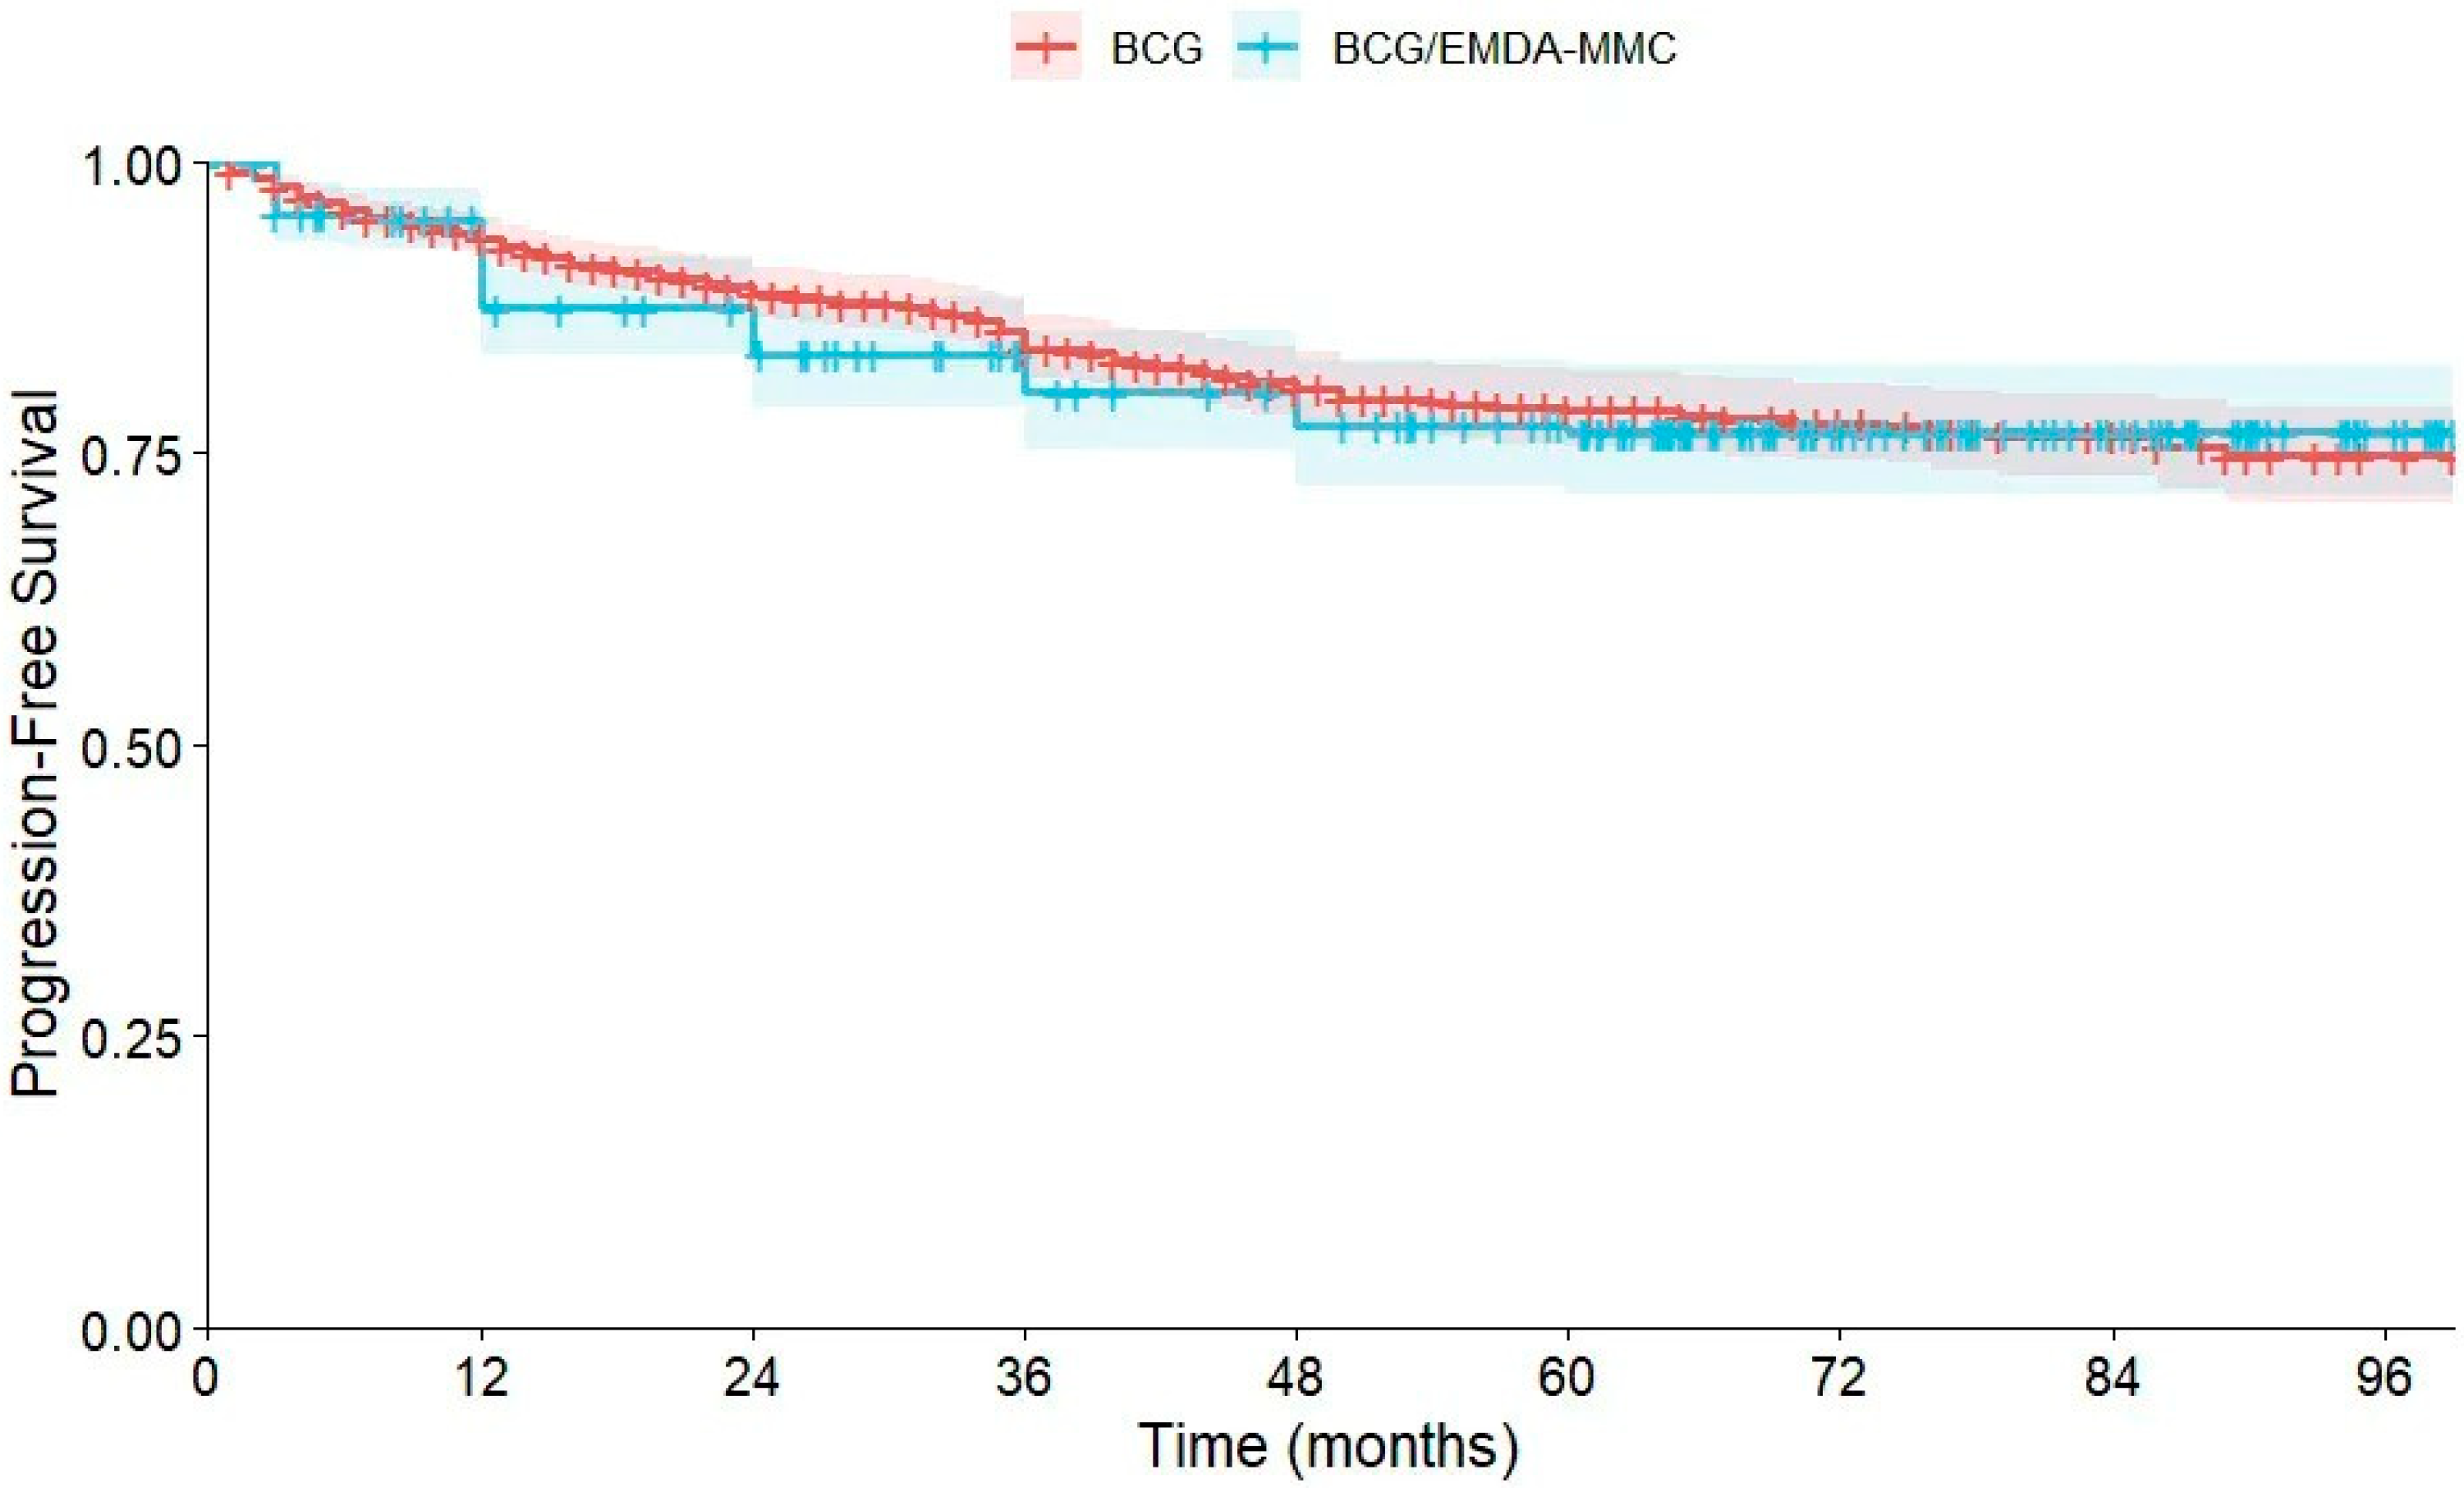
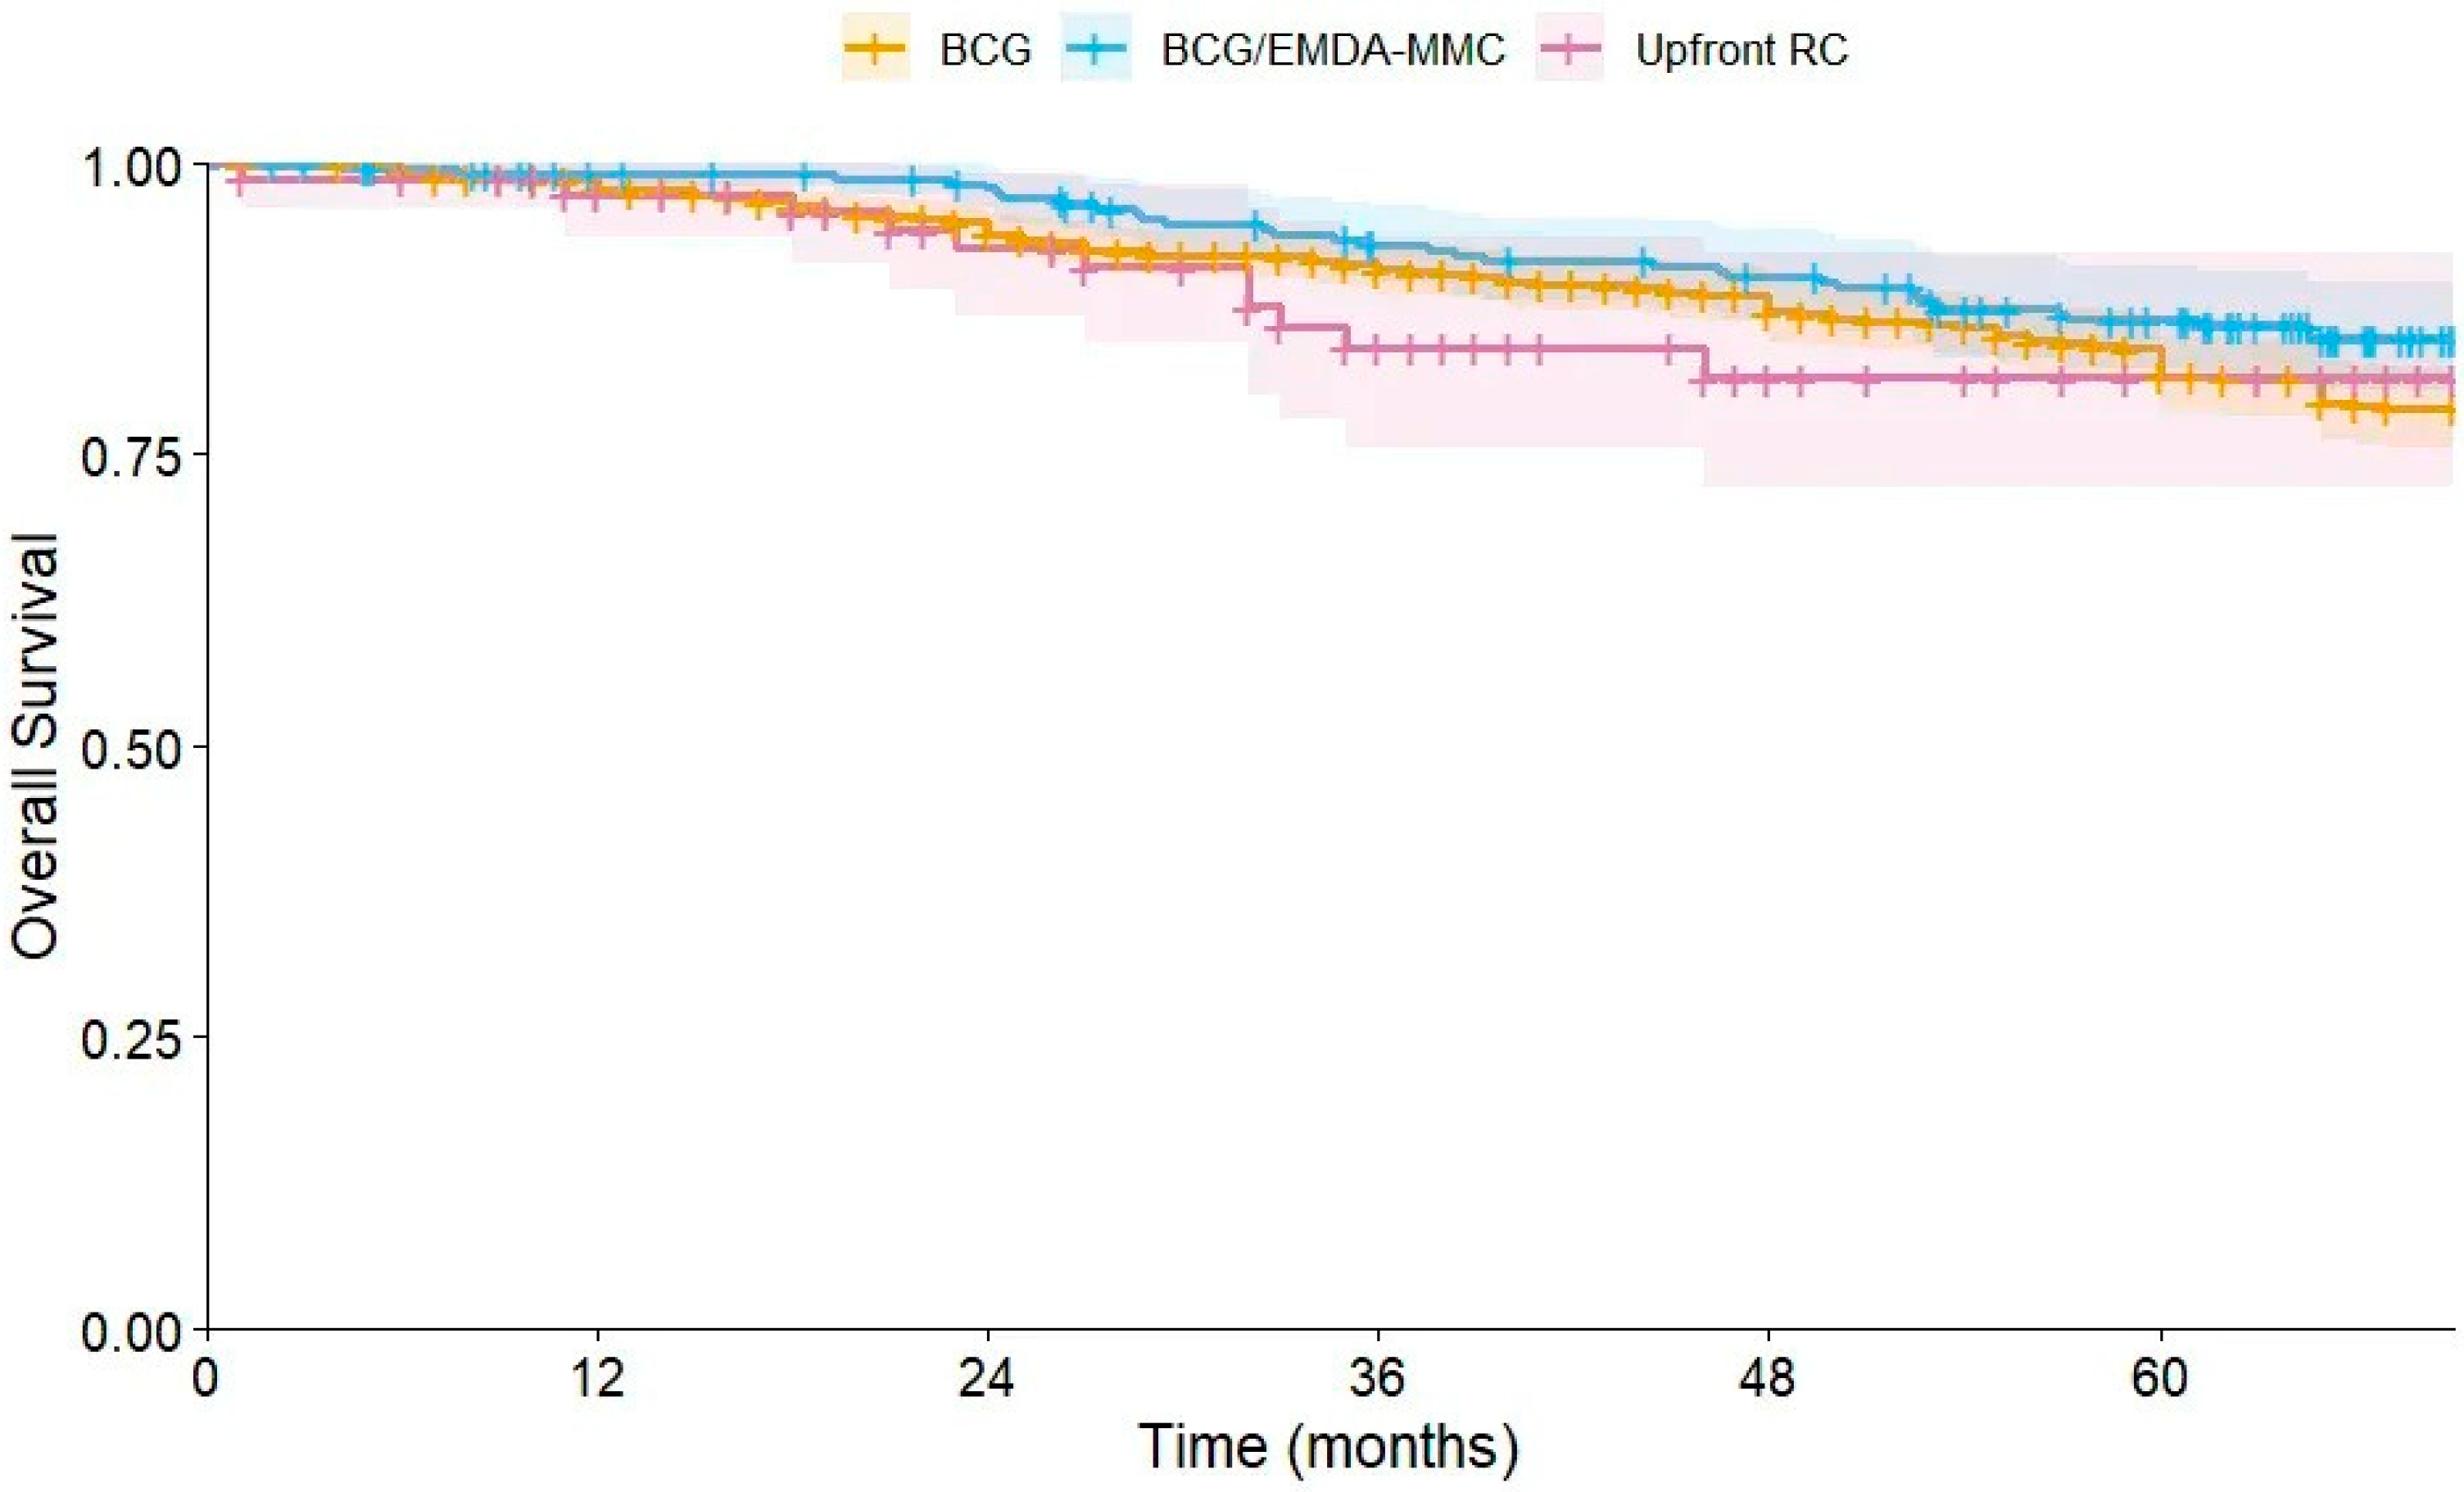
Introduction: Conservative or upfront radical management for high- and very high-risk non-muscle-invasive bladder cancer continues to be debated, particularly for cases with adverse pathological features. We aimed to compare survival outcomes among NMIBC patients treated with transurethral resection of bladder tumour (TURBT) followed by either Bacillus Calmette–Guérin (BCG), sequential BCG plus electromotive administration of mitomycin C (EMDA-MMC), or upfront radical cystectomy (RC). Materials and Methods: High- and- very high-risk NMIBC cases undergoing TURBT followed by BCG, BCG plus EMDA-MMC, or RC at two international tertiary referral centres between 2009 and 2024 were retrospectively reviewed. Recurrence-free survival (RFS), progression-free survival (PFS), and overall survival (OS) were estimated using Kaplan–Meier methods. Multivariable Cox regression models were applied to identify factors independently associated with survival outcomes. Results: A total of 1178 patients were included: 852 received BCG, 249 received BCG/EMDA-MMC, and 77 underwent upfront RC. Kaplan–Meier analysis revealed no significant differences in RFS or PFS between the BCG and BCG/EMDA-MMC groups, nor in OS between the three treatment strategies. According to multivariable analysis, concomitant carcinoma in situ (CIS) and increasing T stage at TURBT were independently associated with poorer RFS (HR 1.39; 95% CI 1.05–1.85), PFS (HR 1.95; 95% CI 1.36–2.82), and OS (HR 2.28; 95% CI 1.60–3.25). A second resection conferred a protective effect on PFS (HR 0.72; 95% CI 0.54–0.95). Treatment modality (BCG, BCG/EMDA-MMC, or upfront RC) was not significantly associated with any survival endpoint. Conclusions: In this large multicentre series of patients with high- and very high-risk NMIBC undergoing TURBT, survival outcomes were primarily influenced by clinical–pathological characteristics rather than the adjuvant treatment of choice.