


Abstract
Background: Yoghurt can modify gastrointestinal disease risk, possibly acting on gut microbiota. Our study aimed at exploring the under-investigated association between yoghurt and gastric cancer (GC). Methods: We pooled data from 16 studies from the Stomach Cancer Pooling (StoP) Project. Total yoghurt intake was derived from food frequency questionnaires. We calculated study-specific odds ratios (ORs) of GC and the corresponding 95% confidence intervals (CIs) for increasing categories of yoghurt consumption using univariate and multivariable unconditional logistic regression models. A two-stage analysis, with a meta-analysis of the pooled adjusted data, was conducted. Results: The analysis included 6278 GC cases and 14,181 controls, including 1179 cardia and 3463 non-cardia, 1191 diffuse and 1717 intestinal cases. The overall meta-analysis revealed no association between increasing portions of yoghurt intake (continuous) and GC (OR = 0.98, 95% CI = 0.94–1.02). When restricting to cohort studies, a borderline inverse relationship was found (OR = 0.93, 95% CI = 0.88–0.99). The adjusted and unadjusted OR were 0.92 (95% CI = 0.85–0.99) and 0.78 (95% CI = 0.73–0.84) for any vs. no yoghurt consumption and GC risk. The OR for 1 category of increase in yoghurt intake was 0.96 (95% CI = 0.91–1.02) for cardia, 1.03 (95% CI = 1.00–1.07) for non-cardia, 1.12 (95% CI = 1.07–1.19) for diffuse and 1.02 (95% CI = 0.97–1.06) for intestinal GC. No effect was seen within hospital-based and population-based studies, nor in men or women. Conclusions: We found no association between yoghurt and GC in the main adjusted models, despite sensitivity analyses suggesting a protective effect. Additional studies should further address this association.
1. Introduction
According to the 2018 World Cancer Research Fund (WCRF), there is strong evidence that high-salt and salt-preserved foods, overweight/obesity and heavy alcohol consumption increase the risk of gastric cancer (GC), while there is some evidence that consumption of grilled or barbecued meat and fish, consumption of processed meat, low intake of fruit and citrus fruit increase GC risk [1]. Data on the association of GC with yoghurt intake is scarce. One issue is the difficulty in collecting adequate information on yoghurt consumption, which is usually reported among dairy products in general or together with other foods [2].
The anti-cancer properties of yoghurt have been described [3]. A recent meta-analysis assessed a protective effect of yoghurt consumption and cancer overall, with significant associations for colorectal and bladder cancer, but did not consider GC [4]. Another review described a protective effect of increasing dairy products and yoghurt consumption on oesophagal and colorectal cancers, reporting non-significant results for GC [5].
Yoghurt can be beneficial towards gastrointestinal disease by acting positively on the gut microbiota [3], balancing inflammation and dysbiosis [6]. The results obtained on the effectiveness of probiotics reducing mucosal damage of hyperacidity and Helicobacter pylori (Hp), possibly contributing to limiting the colonisation of the stomach by the bacterium, suggest a possible protective role of yoghurt towards gastric disease [7,8,9,10]. In particular, natural probiotics present in traditional fermented food may counter the damage exerted by Hp on gastric mucosa [10]. The beneficial properties of fermented food for overall and gastrointestinal health have led to the concept of functional food [11].
Dairy products, and yoghurt in particular, are poorly investigated in relation to GC and are often excluded from meta-analyses on nutritional epidemiology [12]. Their properties have been questioned, but scientific evidence showed overall protective effects towards common chronic diseases and cancer, including GC [12]. The few reviews and meta-analyses which addressed this association provided inconsistent results [13,14,15].
The Stomach Cancer Pooling (StoP) Project Consortium [16] provides a unique opportunity to investigate the association between yoghurt intake and GC in a large population of individuals worldwide. We aimed to investigate the role of yoghurt intake on GC risk, including anatomical and histological subtypes, by pooling data from 16 international studies.
2. Methods
The present study is based on the StoP Project Consortium (http://www.stop-project.org/ (accessed on 15 February 2023)) [16], which includes 34 case-control or nested-within-cohort studies, forming a total of 13,121 cases and 31,420 controls from 14 countries. The StoP Project aims to examine the role of several lifestyle and genetic determinants in the aetiology of gastric cancer through pooled analyses of individual-level data after central collection and validation of the original datasets. Participating studies were involved through the personal contacts of participating investigators. Principal investigators provided a signed data transfer agreement and, thereafter, the original data set of the study. Two studies (one from Greece and one from Finland) computed their own results locally (through standardised analyses) and then provided estimates for the second-stage meta-analysis to the StoP Project consortium [17,18]. The StoP Project received ethical approval from the University of Milan Review Board (19/15 on 1 April 2015). Detailed information on the overall aims and methods has been described elsewhere [19].
The current analysis is based on 16 studies with information on yoghurt intake, including two studies from Italy [20,21], one from Portugal [22], two from Spain [23,24], two from Greece [7,25], one from Finland [18], one from Japan [26], one from Russia [27], three from Mexico [28,29,30], two from the USA [31,32] and one from Brazil [33]. Of these, nine were hospital-based studies, and seven were population-based studies. Of the latter, three were nested in prospective cohorts. The analysis includes histologically-confirmed GC cases; controls were selected based on hospital or neighbourhood. Additional information on the studies’ characteristics are available in Supplementary Table S1.
Data were harmonised according to a pre-specified format, and completeness and consistency between variables were checked. Yoghurt intake was derived for each study using food frequency questionnaire (FFQ) information. In the original data collection, yoghurt intake was collected either in g per day or portions per day, with country-specific variability (e.g., 1 portion = 125 g in Europe, 150 g in the USA and 200 g in Russia). An overall yoghurt intake variable was generated by summing up the different intakes registered in each study, considering as a measurement unit the number of portions per week. A categorical variable was created considering categories of frequency of yoghurt intake (no intake, >0–0.5, >0.5–1.5, >1.5–4.5, and >4.5 portions per week).
First of all, we run a univariate analysis.
Subsequently, multivariable unconditional logistic regression models were used to estimate the odds ratios (OR) of GC and the corresponding 95% confidence intervals (CI) according to yoghurt intake. The logistic regression models included terms for sex, age (≤55, 56–59, 60–64, 65–69, 70–74, 75+ years), smoking status (never, former, current smoker), socioeconomic status (study-specific low, intermediate, high as defined in each original study based on education, income or occupation), alcohol drinking (never, low: ≤12 g/day, intermediate: 13–47 g/day, high: >47 g/day) and vegetable and fruit intake (low, medium, high defined by study-specific tertiles). A model using the categorical variable for yoghurt was also adjusted for the study centre. This model was fitted on pooled data from 12 studies which shared the full data. An OR estimate for yoghurt intake as a continuous variable was obtained for each of the 16 studies, and then a combined OR was obtained using a random-effect meta-analysis [34]. We chose a two-stage model because of the heterogeneity in the methodology used in the studies included in the pooled analysis. We also performed analyses by anatomical subsite and histological type. Several stratified analyses were run, namely by sex, study design (hospital-based vs. population-based) and geographic region. Moreover, a meta-analysis restricted to the three case-control studies nested in cohorts was also performed, because of the high validity of the results from this type of study.
Also, we performed a sensitivity analysis by adding a term for total calorie intake to the main model. This analysis was restricted to 10 studies with available information on both yoghurt and caloric intake.
The main model was also repeated by using yoghurt intake as a dichotomous variable (no/any weekly intake).
Heterogeneity between strata-specific results was assessed using the Q test.
A p-value less than 0.05 was considered statistically significant All the statistical analyses were performed on STATA, version 16.1 (Stata Corp., College Station, TX, USA) [35].
3. Results
The analysis included 20,459 subjects, comprising 6278 cases and 14,181 controls. Table 1 shows their distribution by study, sex, age and major covariates. Most of the individuals were of low socioeconomic status (46.9% and 36.9%). Also, cases were more frequently tobacco smokers (23.3% vs. 20.4%) and heavy alcohol drinkers (14.4% vs. 9.8%), while they consumed fewer vegetables and fruits (33.1% vs. 36.1%) than controls. Overall, 21.9% of cases and 9.2% of controls reported a history of GC among first-degree relatives.
Table 1.
Distribution of cases of gastric cancer and controls according to sex, age and selected covariates.
Table 2 presents the results of the main analysis. The univariate analysis showed a significant inverse relationship between increasing portions of yoghurt per week and GC risk (OR = 0.93, 95% CI = 0.91–0.96).
Table 2.
Odds ratios (OR) and 95% confidence intervals (CI) of the association between portions of yoghurt intake per week and gastric cancer (GC), based on the study [21,22,23,24,25,26,27,28,29,31,32,33].
In the adjusted model, the association between yoghurt intake and GC was not linear across categories of intake, and no relationship was found by using yoghurt intake as a continuous variable (OR = 1.00, 95% CI = 0.97–1.03) based on 12 studies. When a dichotomous variable for yoghurt intake was used, we observed an inverse association between any yoghurt intake vs. no yoghurt intake and GC risk (OR = 0.92, 95% CI = 0.85–0.99). The association was similar when the analysis was restricted to the three cohort studies (not shown in detail).
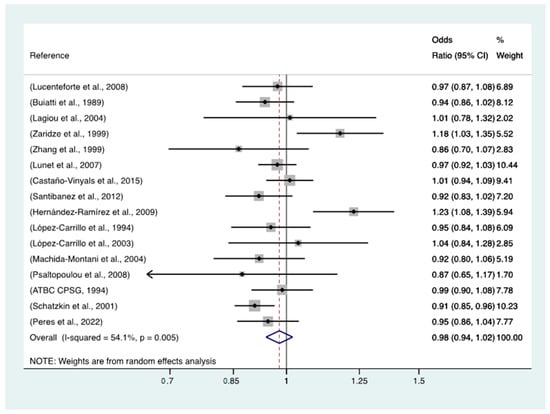
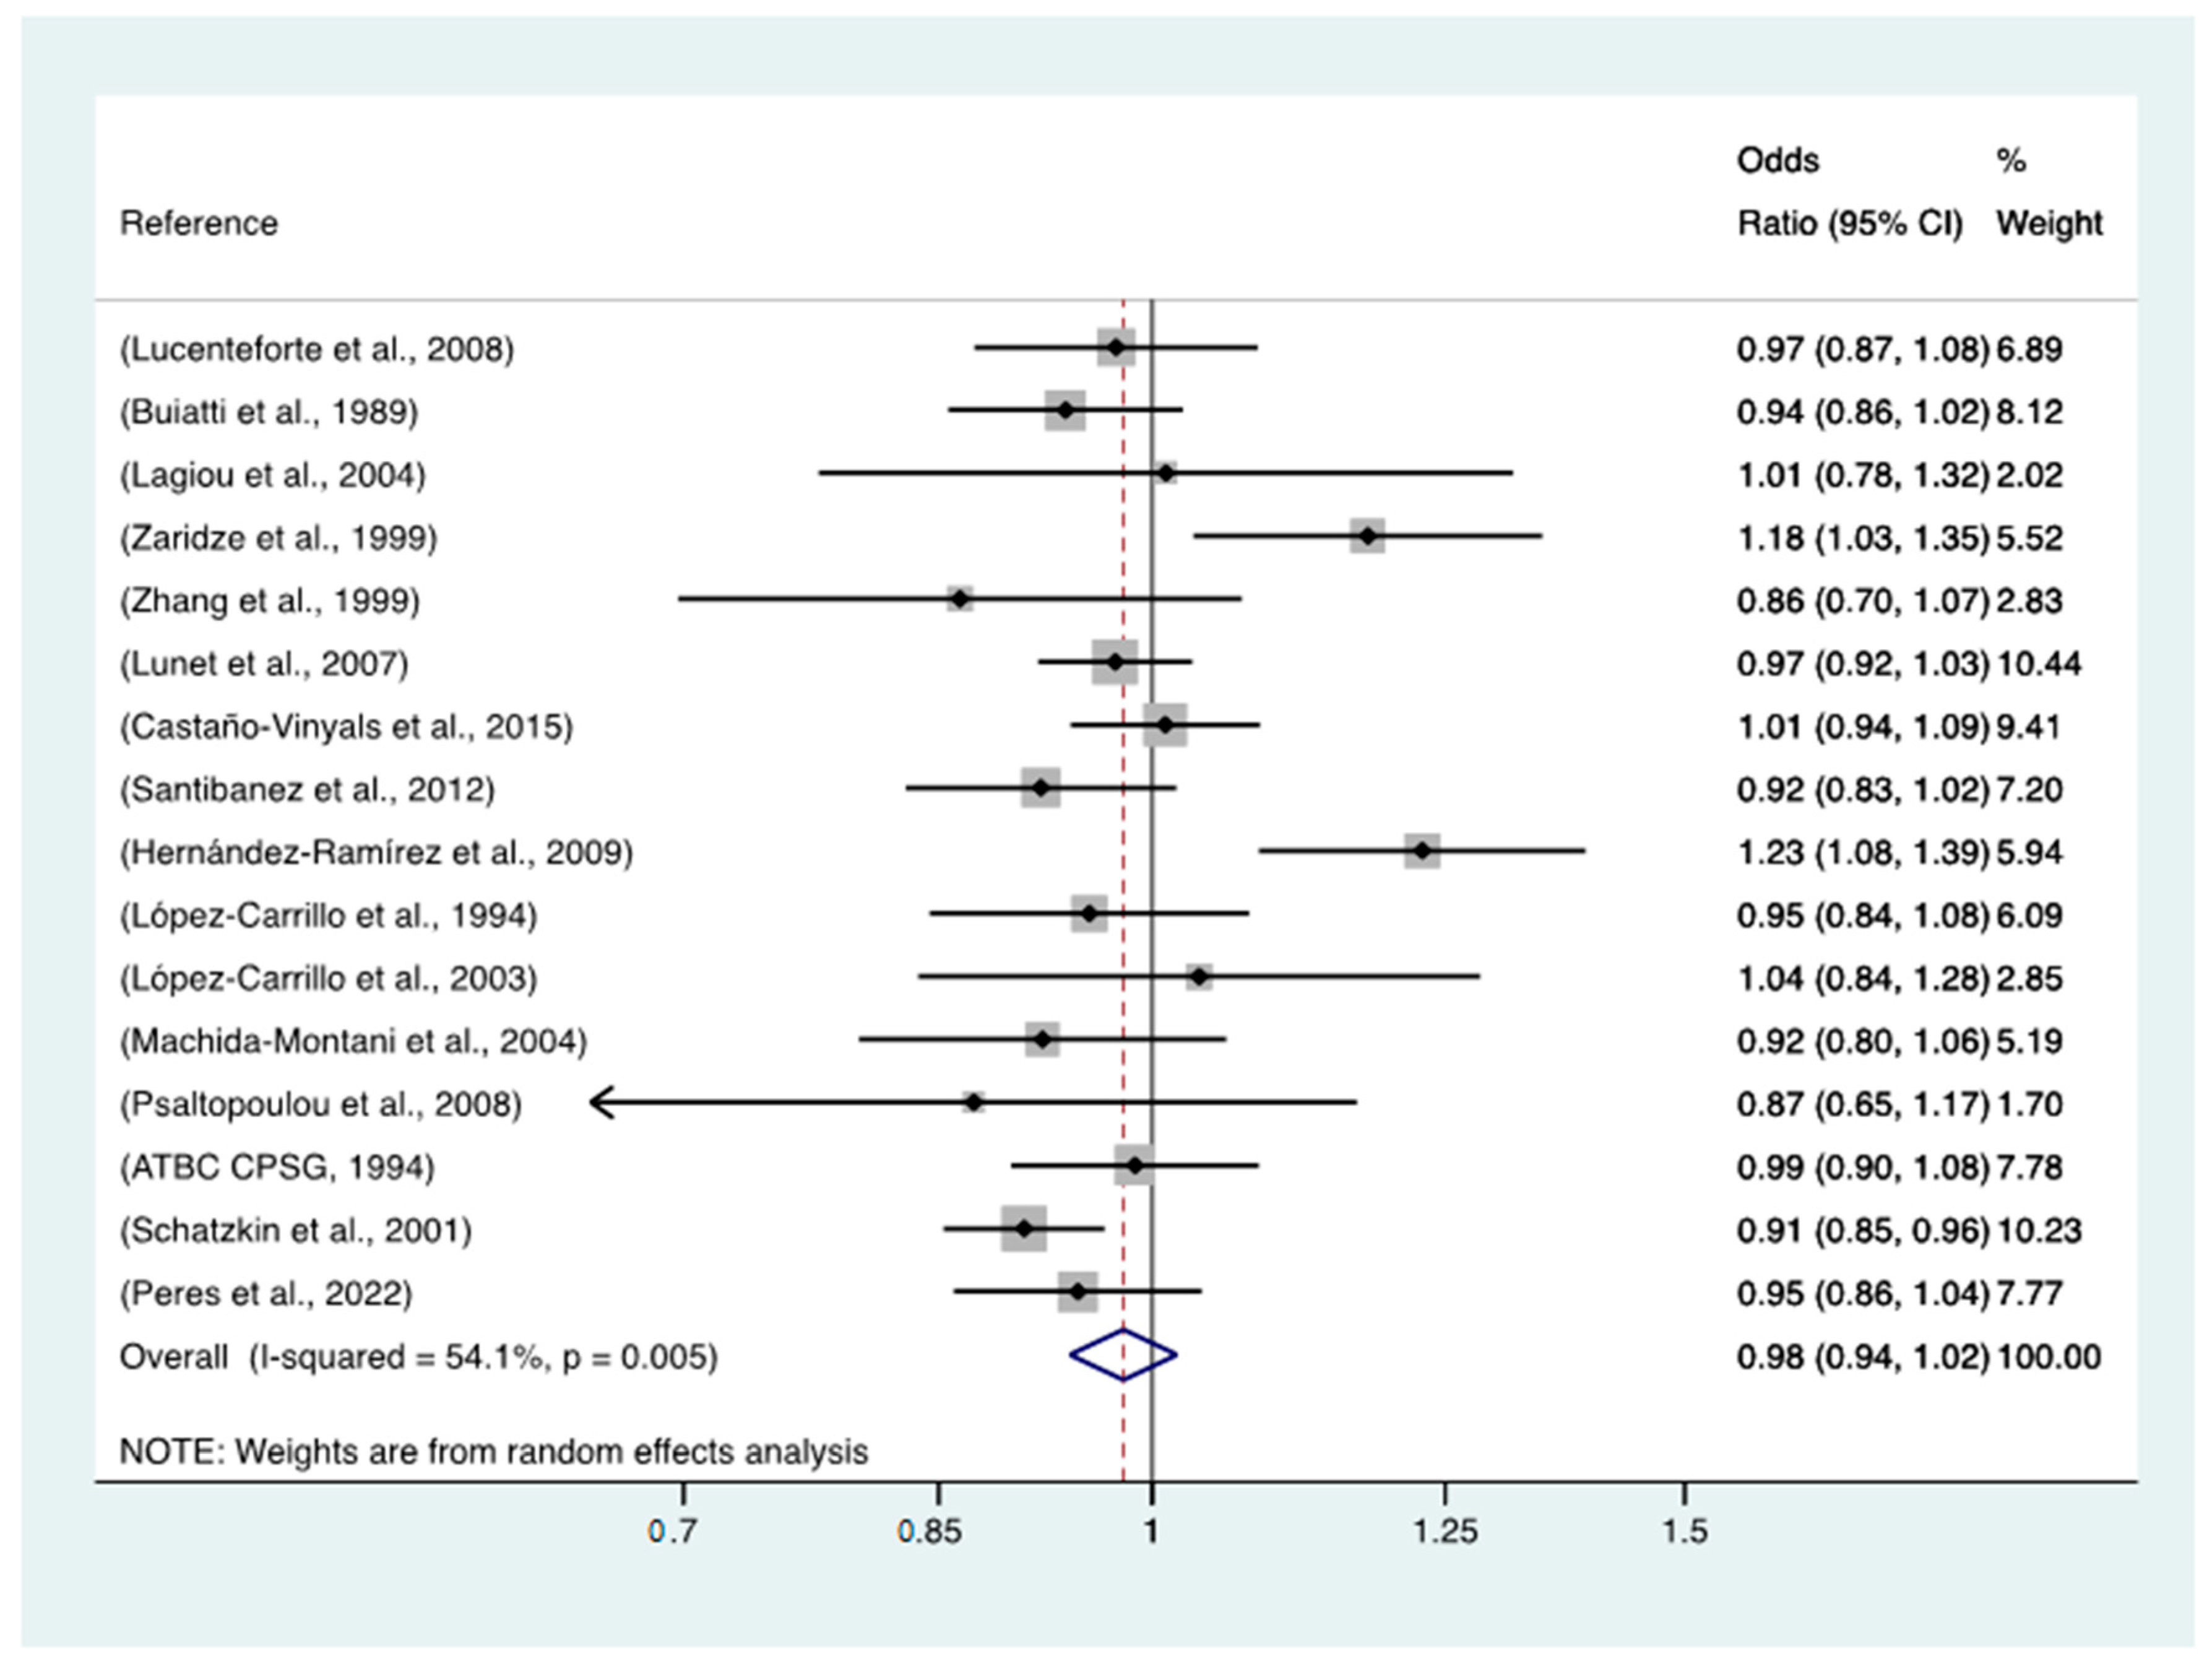
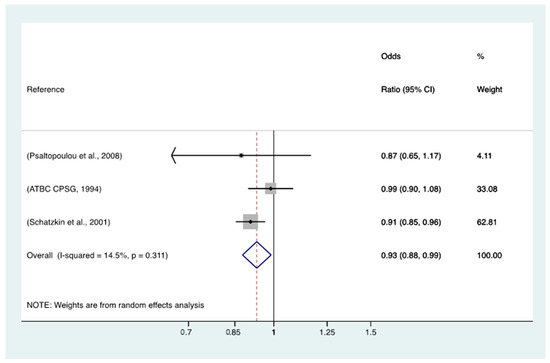
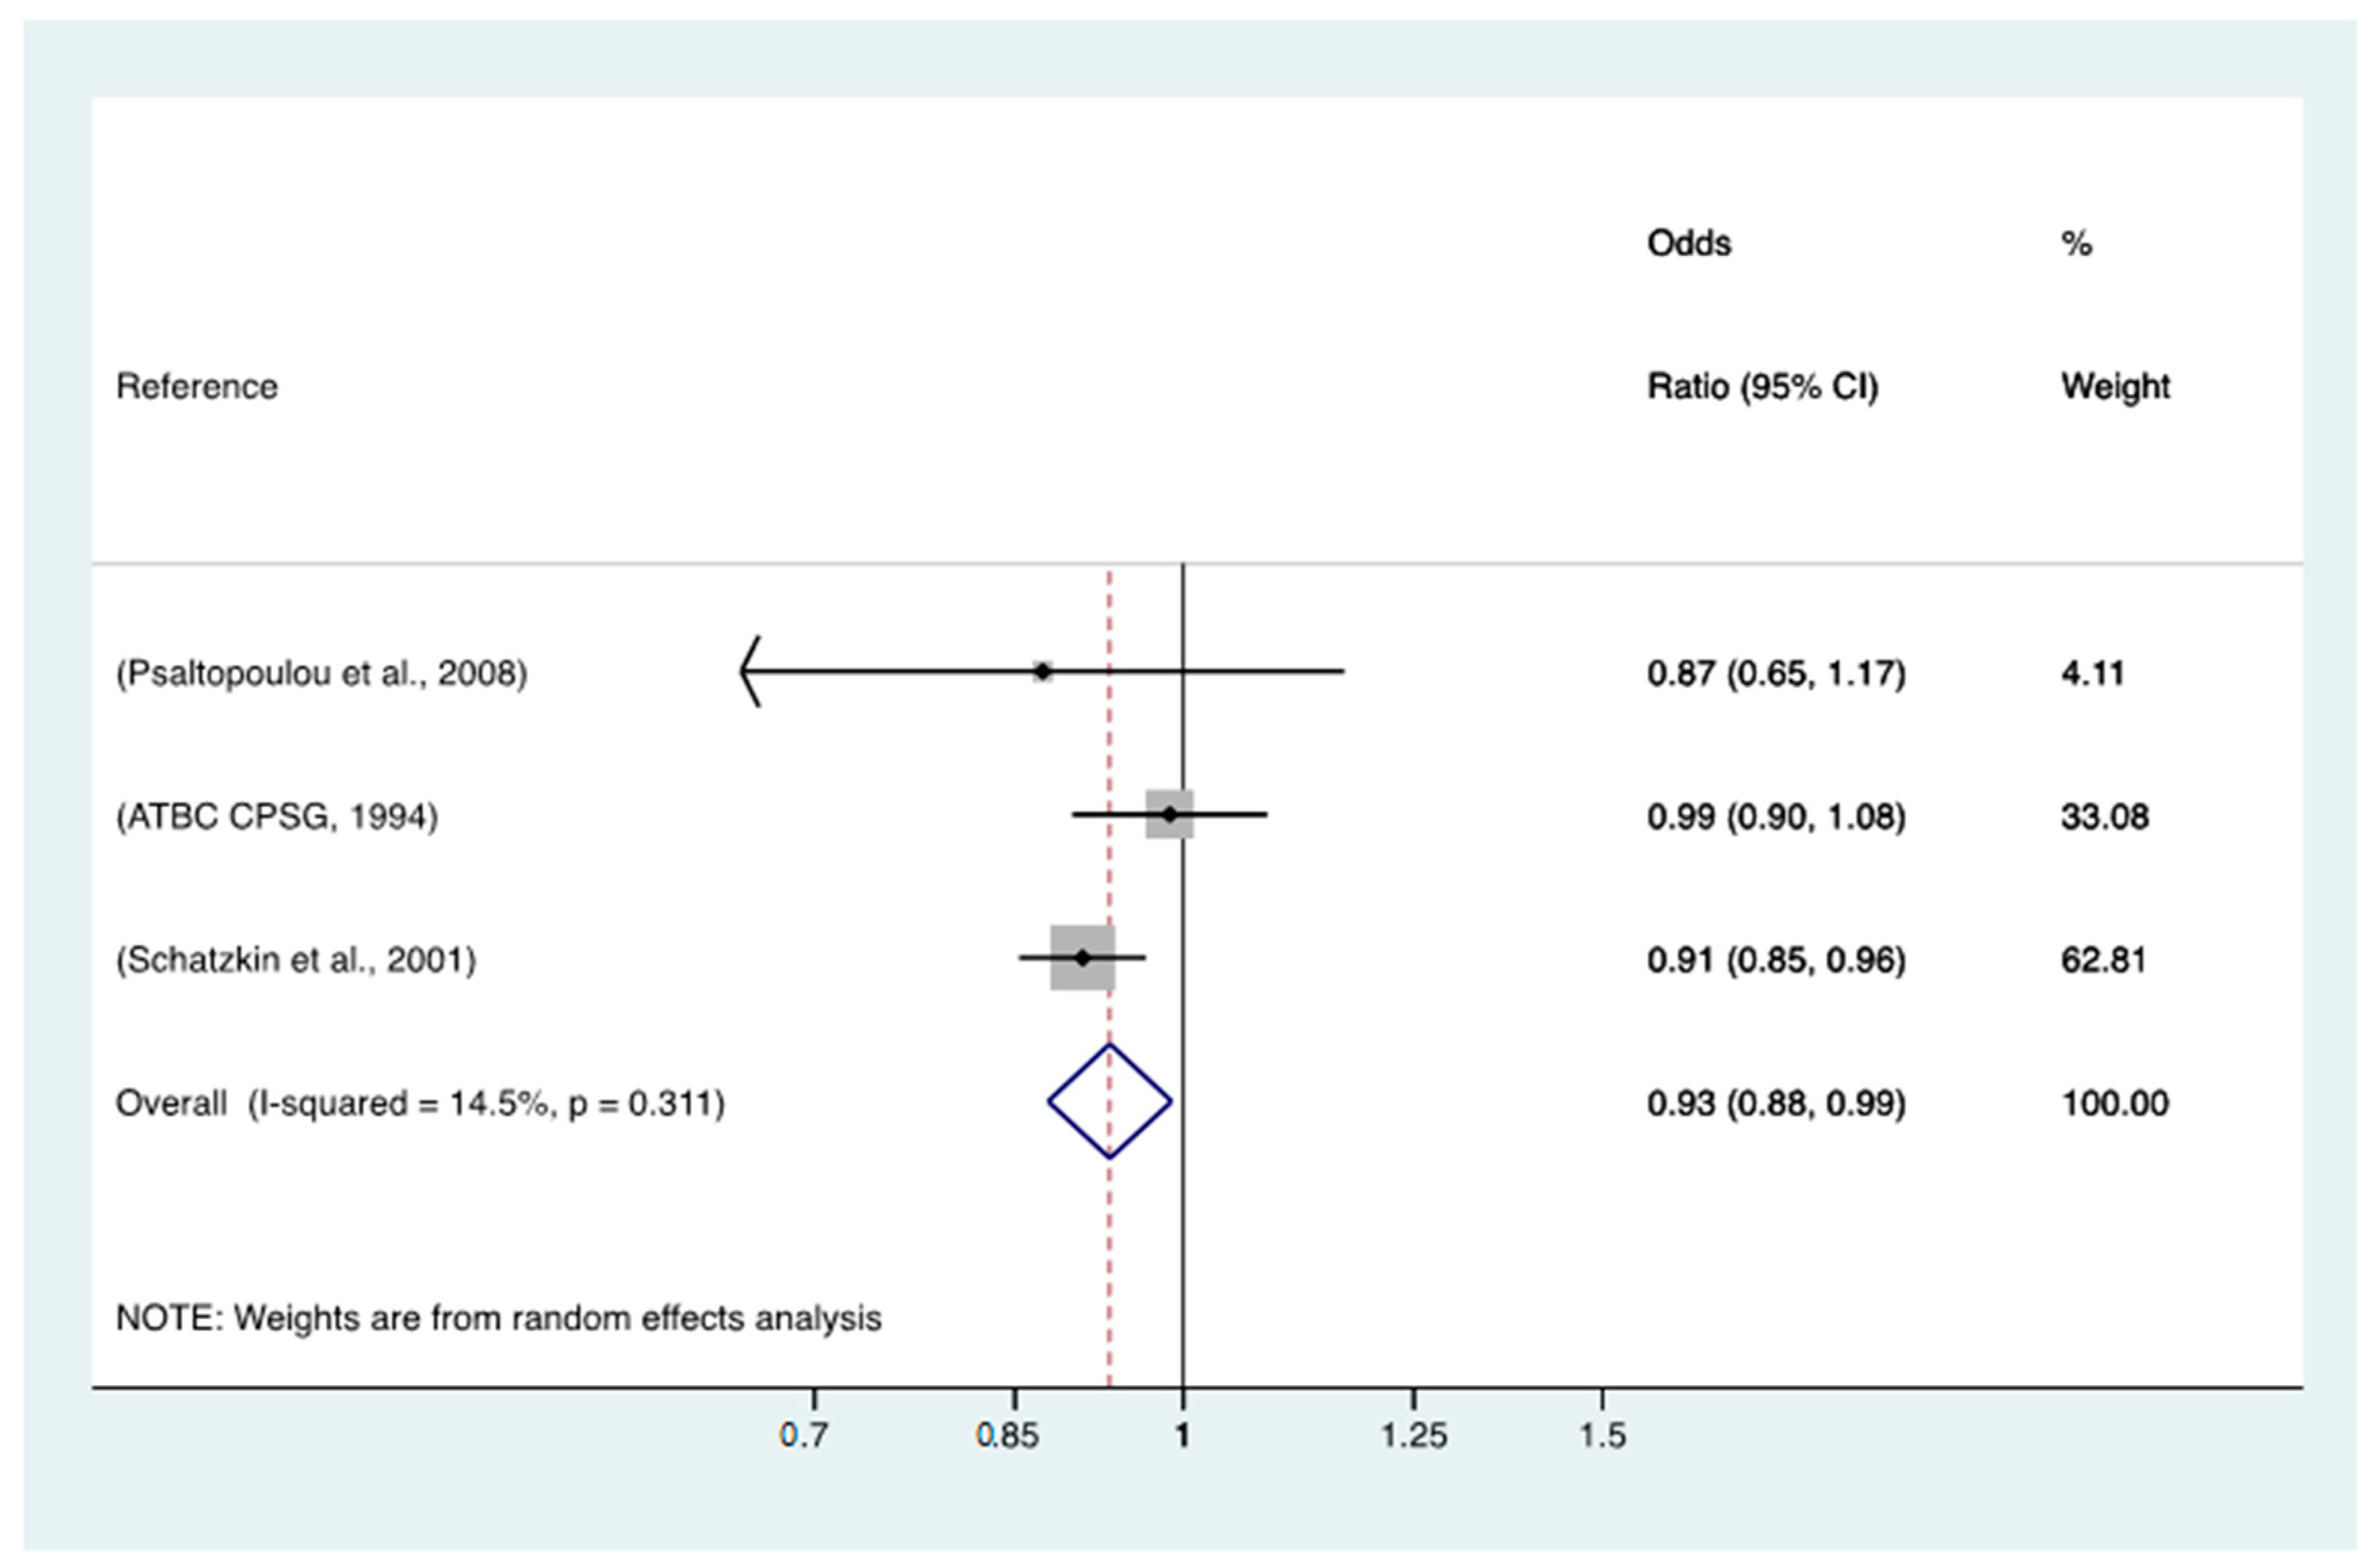
The meta-analysis of all 16 studies (Figure 1) revealed a non-significant association between yoghurt intake and GC, with an OR of 0.98 (95% CI = 0.94–1.02, p heterogeneity = 0.005) for the highest category of intake vs. no yoghurt consumption. When the meta-analysis was restricted to the three case-control studies nested in cohort studies (Figure 2), a significant inverse relationship was found, with an OR of 0.93 (95% CI = 0.88–0.99, p heterogeneity = 0.311).
Figure 1.
Results of a meta-analysis of the studies included. Notes: ATBC CPSG = The alpha-tocopherol beta carotene Cancer Prevention Study Group. Meta-analysis of the results for portions of yoghurt intake per week is continuous [17,18,20,21,22,23,24,25,26,27,28,29,30,31,32,33].
Figure 2.
Results of the meta-analysis restricted to the cohort studies included. Notes: ATBC CPSG = The alpha-tocopherol beta carotene Cancer Prevention Study Group. Meta-analysis of the results for portions of yoghurt intake per week is continuous [17,18,32].
Table 3 reports the results by GC anatomical subsite and histological type. A linear inverse relationship was suggested for cardia GC (OR = 0.96, 95% CI = 0.90–1.02), while a direct relationship emerged for non-cardia GC (OR = 1.03, 95% CI = 1.00–1.07), and no relationship was identified for the undefined subsite GC cases (OR = 1.02, 95% CI = 0.96–1.08). These results were not significantly heterogeneous (p for heterogeneity = 0.15). Also, a significant positive trend was found for diffuse GC when considering an increase in intake of one portion of yoghurt per week (OR = 1.12, 95% CI = 1.07–1.19), no relationship was found with intestinal GC (OR = 1.02, 95% CI = 0.97–1.06), and GC of undefined histology was inversely related to yoghurt consumption (OR = 0.95, 95% CI = 0.91–1.00), with significant heterogeneity among these values (p for heterogeneity < 0.001).
Table 3.
Odds ratios (OR) and 95% confidence intervals (CI) of the association of yoghurt intake by approximate portions of yoghurt intake and GC subsites and histological types.
Table 4 reports the results of the analysis stratified by study design. No significant association was found in hospital-based as well as population-based studies, without significant heterogeneity (p = 0.736).
Table 4.
Odds ratios (OR) and 95% confidence intervals (CI) of the association of yoghurt intake by approximate portions of yoghurt intake and study design.
Additional exploratory analyses by geographic region were limited by the small number of available studies and did not offer further insight into the results.
No effect modification by sex was revealed (p = 0.3) (Supplementary Table S2).
No differences were evidenced between the analysis adjusted and unadjusted by caloric intake.
4. Discussion
Our pooled analysis of 16 international studies found no association between yoghurt intake and GC risk. Results were consistent across sex, anatomical subsite and histology groups. The analysis restricted to cohort studies showed a moderate inverse relationship between yoghurt intake and GC, while no association was found in hospital-based and population-based case-control studies.
While total yoghurt intake was lower among cases than controls, adjusted analyses from logistic regression models did not find an association between yoghurt intake and GC risk. This is mainly due to unbalances in the case:control ratio across studies with a different mean level of yoghurt intake. In fact, the analysis based on univariate models (only adjusted by the study) showed a significant inverse association between any yoghurt intake and GC risk. It is possible that yoghurt consumption may affect GC risk only at higher intakes than those considered in the present pooled analysis [36]. Energy intake was not a confounder in this study, as demonstrated by the sensitivity analyses performed among 10 studies with the available information. This is consistent with the hypothesis that yoghurt consumers do not present any particular pattern of caloric intake.
Noticeably, when considering yoghurt intake as a dichotomous variable, GC risk resulted in being significantly decreased, which supports the evidence of healthy properties of yoghurt.
There is large variability of locally consumed fermented foods and beverages, which may lead to different effects on human health in different populations. Most traditional fermented foods are natural sources of probiotic microbes, which have been shown to have anti-Hp properties. As pointed out by Nair and coworkers, the geographical difference in GC incidence among countries with a high prevalence of Hp infection (e.g., low GC rates in Africa and India vs. high GC rates in Japan) is not fully explained by the virulence of different Hp strains [10]. The authors hypothesised that the differences in GC epidemiology in these high Hp-risk countries might be partially explained by different patterns of consumption of fermented foods due to the microbial content in ethnic fermented food acting against Hp-induced carcinogenesis [10].
Probiotics have been shown to be effective against different GI diseases, including Hp infection [37]. For example, probiotic supplements may improve the Hp eradication rate [38,39,40]. A study conducted in China on more than 2000 people aged 0 to 77 years found that individuals who reported consuming yoghurt frequently or daily had a lower risk of Hp infection than never or occasional consumers (OR: 0.80, 95% CI: 0.65–1.00), especially restricting the analysis to adults [41]. As reviewed by Scourboutakos et al., yoghurt containing Lactobacillus casei DN-114001 is associated with decreased frequency of common respiratory infectious diseases, reduced risk of Clostridium difficile and antibiotic-associated diarrhoea in the elderly, and decreased asthma and rhinitis episodes in children [42]. Another bacterial strain, Bifidobacterium lactis BB12, was associated with increased gastrointestinal well-being, in particular, reducing abdominal bloating, flatulence and discomfort symptoms [42]. Also, the properties conferred by the combination of different microorganisms have been studied, such as that of Bifidobacterium lactis BB12 plus Lactobacillus acidophilus LA-5, which, at dosage similar to those of commercial products, improved metabolic parameters (e.g., glycemic control and blood lipids) and antioxidant status in diabetics [42]. The probiotic strain combination has been demonstrated to produce a higher quality yoghurt [43], changing its nutritional composition [43]. For example, Lactobacillus acidophilus and Bifidobacterium bifidum are associated with higher moisture and low calorie, while Lactobacillus plantarum and Lactobacillus casei determine higher ash, protein, carbohydrate, energy, calcium and phosphorous content in yoghurt [43]. Also, a different combination of microorganisms acts on the acid and bile salt tolerance, which are important for the survival duration of the live bacteria from yoghurt in the gut [43]. It is important to consider that non-industrial yoghurt may contain different species of bacteria than Lactobacillus and Bifidobacterium, although specific data are scarce [44,45].
Next to the effect conveyed by fermentation of live bacteria, the yoghurt matrix contains other classes of nutrients which may exert a beneficial effect, including vitamins and minerals (e.g., calcium and vitamin D), bioactive fatty acids, and proteins such as whey [46].
Nutritional cancer epidemiology often lacks investigation on dairy products and yoghurt in particular, and available studies show inconsistent results [13,14,15]. A meta-analysis by Sun and coauthors [14] suggested an inverse relationship between yoghurt intake and GC risk despite no significant result, based on three case-control studies and one cohort study (RR = 0.77 for highest vs. lowest yoghurt consumption, 95% CI = 0.58–1.03, p for heterogeneity = 0.891 < Egger’s test: p = 0.923). The authors found similar results among European and Asian studies and by study design [14]. Another meta-analysis conducted in the same period did not identify any effect of fermented (yoghurt, cheese) and non-fermented (milk) dairy products on GC risk [15]. The research focused on gut microbiota may provide a better understanding of the potential effects of fermented foods such as yoghurt on GC risk [6].
Consistent with our results, a meta-analysis by Guo and coworkers found an inverse association between dairy products intake and GC risk in cohort studies (RR = 0.76 for highest vs. lowest category of total dairy intake 95% CI: 0.64–0.91, based on six cohort studies) but no association in case-control studies [47]. Prospective cohort studies provide more reliable data on lifestyle habits [48]. Moreover, both cohort and case-control studies may fail in reconstructing a comprehensive picture of the dietary habits of the participants, which are largely subjected to changes, and whose effect on health outcomes are mostly seen over the long period [49,50]. The difference we found between the study design (case-control vs. cohort) may reflect the different timing in data collection rather than the different structure of the questionnaires used, namely data collected at baseline vs. data collected at the moment of a cancer diagnosis. No significant difference was found between hospital-based and population-based case-control studies. In this sense, the lack of difference we obtained supports the hypothesis of no relationship between yoghurt and GC.
No specific relationship emerged by anatomical subsite of GC, nor effect modification by sex. This corroborates the hypothesis of the lack of any effect of yoghurt on GC overall. The result we obtained when stratifying by histological type needs to be considered with caution: while a positive association was identified for diffuse GC, an inverse one was observed when considering cases undefined for histological type, suggesting that their redistribution among diffuse and intestinal type would lead to no overall association. It should be considered that data collection on GC epidemiology, including pathology data, is widely heterogeneous among different countries [51] and among different regions of the same country.
We could not identify other studies reporting comparable results for yoghurt intake and anatomical or histological types of GC, limiting the interpretability of the results.
Our pooled analysis has several strengths, starting from a large number of studies included. Notably, by pooling data from the participants of the StoP-Consortium, we could address a topic which has to date been poorly investigated. We could account for several potential confounders, given the detailed information available in the dataset.
This study also suffers from some limitations. The measure we used was the frequency of yoghurt intake, but portion size can vary by country (e.g., one portion was equal to 125 g in most studies but was equal to 200 g in the Russian study). Also, we did not adjust for Hp infection, which is an important risk factor of GC, because of missing data. Further, analyses by anatomical subsite and histological type were impaired by the high proportion of unclassified cases, limiting the interpretability of the results we obtained. In addition, most of the included studies had a case-control design, where questionnaires are administered at the moment of cancer diagnosis among the cases, potentially introducing differential recall bias.
In addition, we could not account for the fact that yoghurt may vary according to the matrix and milk source (e.g., cow or goat). Further, data were too sparse to investigate any difference between different types of yoghurt, including flavoured, frozen, whole milk or low-fat yoghurt. Lastly, while some studies were designed to investigate diet and GC, none were specifically focused on yoghurt. The study was not designed to investigate the role of the type of milk used for yoghurt production (raw, pasteurised, powder), the type and number of microorganisms used in the coagulation process, as well as the time and incubation temperature or additional ingredients (juices, fruits, starch, texturising agents, protein, etc.) that are incorporated during the production steps.
In conclusion, this pooled analysis found no association between yoghurt intake and GC, nor significantly different effects within the anatomical sites or histological types. Cohort studies, as well as analyses treating yoghurt consumption as a dichotomous variable, showed an inverse association between yoghurt intake and GC risk, suggesting that a healthy effect of yoghurt may be evidenced in large prospective studies. The variability in yoghurt composition is an inherent characteristic of this product, which complicates the identification of its effects on human health. Therefore, we recommend caution in interpreting our results, given the lack of information on yoghurt characteristics and composition, which may vary in different populations. The association between yoghurt and GC deserves further investigation, given the potential implication in GC prevention.
Supplementary Materials
The following supporting information can be downloaded at: https://www.mdpi.com/article/10.3390/nu15081877/s1, Table S1: Characteristics of StoP Consortium Studies. Table S2: Results of the analysis stratified by sex.
Author Contributions
Conceptualization, G.C. and P.B.; methodology, G.C., P.B. and C.P.; formal analysis, G.C., P.B., C.S.R., S.J.W. and A.T.; investigation, all the authors; resources, C.L.V. and E.N.; data curation, C.P.; writing—original draft preparation, G.C.; writing—review and editing, all the authors, with substantial contribution by M.C.C., S.M. and S.J.W.; supervision, P.B.; project administration, C.L.V.; funding acquisition, C.L.V. All authors have read and agreed to the published version of the manuscript.
Funding
This study was supported by the Associazione Italiana per la Ricerca sul Cancro (AIRC), Project no. 21378 (Investigator Grant). N.L. and S.M. are funded under the Unidade de Investigação em Epidemiologia—Instituto de Saúde Pública da Universidade do Porto (EPIUnit; UIDB/04750/2020) financed by national funds from the Foundation for Science and Technology—FCT (Portuguese Ministry of Science, Technology and Higher Education). S.M. also received funding under the scope of the project ‘NEON-PC—Neuro-oncological complications of prostate cancer: longitudinal study of cognitive decline’ (POCI-01-0145-FEDER-032358; Ref. PTDC/SAU-EPI/32358/2017) funded by FEDER through the Operational Program Competitiveness and Internationalisation, and national funding from FCT, and the EPIunit—Junior Research—Prog Financing (UIDP/04750/2020). The Brazilian study FAPESP “Epidemiology and Genomics of Gastric Adenocarcinomas in Brazil” was funded by the Fundação de Amparo à Pesquisa do Estado de São Paulo-FAPESP under process 2014/26897-0. The authors thank the European Cancer Prevention Organization for providing support for the project meetings. This study was partially funded by the Intramural Program of the National Cancer Institute, United States.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
The study was based on the secondary use of de-identified data and was considered exempt by the International Review Board of the University of Bologna.
Data Availability Statement
Data can be obtained from the StoP Project according to the provisions set up in the Consortium (http://stop-project.org/, accessed on 5 December 2022). Further information is available from the corresponding author upon request.
Conflicts of Interest
The authors declare no conflict of interest.
References
- World Cancer Research Fund International. Diet, Nutrition, Physical Activity and Cancer: A Global Perspective—The Third Expert Report; World Cancer Research Fund International: London, UK, 2018; Available online: https://www.wcrf.org/dietandcancer (accessed on 3 December 2022).
- Agudo, A.; Cayssials, V.; Bonet, C.; Tjønneland, A.; Overvad, K.; Boutron-Ruault, M.C.; Affret, A.; Fagherazzi, G.; Katzke, V.; Schübel, R.; et al. Inflammatory potential of the diet and risk of gastric cancer in the EuropeanProspective Investigation into Cancer and Nutrition (EPIC) study. Am. J. Clin. Nutr. 2018, 107, 607–616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Aryana, K.J.; Olson, D.W. A 100-Year Review: Yogurt and other cultured dairy products. J. Dairy Sci. 2017, 100, 9987–10013. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, K.; Dai, H.; Liang, W.; Zhang, L.; Deng, Z. Fermented dairy foods intake and risk of cancer. Int. J. Cancer 2019, 144, 2099–2108. [Google Scholar] [CrossRef] [Scilit]
- Jeyaraman, M.M.; Abou-Setta, A.M.; Grant, L.; Farshidfar, F.; Copstein, L.; Lys, J.; Gottschalk, T.; Desautels, D.; Czaykowski, P.; Pitz, M.; et al. Dairy product consumption and development of cancer: An overview of reviews. BMJ Open 2019, 9, e023625. [Google Scholar] [CrossRef] [Scilit]
- Stiemsma, L.T.; Nakamura, R.E.; Nguyen, J.G.; Michels, K.B. Does Consumption of Fermented Foods Modify the Human Gut Microbiota? J. Nutr. 2020, 150, 1680–1692. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, Y.J.; Sheu, B.S. Probiotics-containing yogurts suppress Helicobacter pylori load and modify immune response and intestinal microbiota in the Helicobacter pylori-infected children. Helicobacter 2012, 17, 297–304. [Google Scholar] [CrossRef] [Scilit]
- Uchida, M.; Shimizu, K.; Kurakazu, K. Yogurt containing Lactobacillus gasseri OLL 2716 (LG21 yogurt) accelerated the healing of acetic acid-induced gastric ulcer in rats. Biosci. Biotechnol. Biochem. 2010, 74, 1891–1894. [Google Scholar] [CrossRef] [Scilit]
- Koga, Y.; Ohtsu, T.; Kimura, K.; Asami, Y. Probiotic L. gasseri strain (LG21) for the upper gastrointestinal tract acting through improvement of indigenous microbiota. BMJ Open Gastroenterol. 2019, 6, e000314. [Google Scholar] [CrossRef] [Scilit]
- Nair, M.R.; Chouhan, D.; Sen Gupta, S.; Chattopadhyay, S. Fermented Foods: Are They Tasty Medicines for Helicobacter pylori Associated Peptic Ulcer and Gastric Cancer? Front. Microbiol. 2016, 7, 1148. [Google Scholar] [CrossRef] [Scilit]
- Maldonado Galdeano, C.; Novotny Nuñez, I.; Carmuega, E.; de Moreno de LeBlanc, A.; Perdigón, G. Role of probiotics and functional foods in health: Gut immune stimulation by two probiotic strains and a potential probiotic yoghurt. Endocr. Metab. Immune Disord. Drug Targets 2015, 15, 37–45. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Poorolajal, J.; Moradi, L.; Mohammadi, Y.; Cheraghi, Z.; Gohari-Ensaf, F. Risk factors for stomach cancer: A systematic review and meta-analysis. Epidemiol Health 2020, 42, e2020004. [Google Scholar] [CrossRef] [Scilit]
- Thorning, T.K.; Raben, A.; Tholstrup, T.; Soedamah-Muthu, S.S.; Givens, I.; Astrup, A. Milk and dairy products: Good or bad for human health? An assessment of the totality of scientific evidence. Food Nutr. Res. 2016, 60, 32527. [Google Scholar] [CrossRef] [Scilit]
- Sun, Y.; Lin, L.J.; Sang, L.X.; Dai, C.; Jiang, M.; Zheng, C.Q. Dairy product consumption and gastric cancer risk: A meta-analysis. World J. Gastroenterol. 2014, 20, 15879–15898. [Google Scholar] [CrossRef] [Scilit]
- Tian, S.B.; Yu, J.C.; Kang, W.M.; Ma, Z.Q.; Ye, X.; Cao, Z.J. Association between dairy intake and gastric cancer: A meta-analysis of observational studies. PLoS ONE 2014, 9, e101728. [Google Scholar] [CrossRef] [Scilit]
- Available online: http://www.stop-project.org/ (accessed on 14 December 2022).
- Psaltopoulou, T.; Kyrozis, A.; Stathopoulos, P.; Trichopoulos, D.; Vassilopoulos, D.; Trichopoulou, A. Diet, physical activity and cognitive impairment among elders: The EPIC-Greece cohort (European Prospective Investigation into Cancer and Nutrition). Public Health Nutr. 2008, 11, 1054–1062. [Google Scholar] [CrossRef] [Scilit]
- The ATBC Cancer Prevention Study Group. The alpha-tocopherol, beta-carotene lung cancer prevention study: Design, methods, participant characteristics, and compliance. Ann. Epidemiol. 1994, 4, 1–10. [Google Scholar] [CrossRef] [Scilit]
- Pelucchi, C.; Lunet, N.; Boccia, S.; Zhang, Z.F.; Praud, D.; Boffetta, P.; Levi, F.; Matsuo, K.; Ito, H.; Hu, J.; et al. The stomach cancer pooling (StoP) project: Study design and presentation. Eur. J. Cancer Prev. 2015, 24, 16–23. [Google Scholar] [CrossRef] [Scilit]
- Lucenteforte, E.; Scita, V.; Bosetti, C.; Bertuccio, P.; Negri, E.; La Vecchia, C. Food groups and alcoholic beverages and the risk of stomach cancer: A case-control study in Italy. Nutr. Cancer 2008, 60, 577–584. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Buiatti, E.; Palli, D.; Decarli, A.; Amadori, D.; Avellini, C.; Bianchi, S.; Biserni, R.; Cipriani, F.; Cocco, P.; Giacosa, A.; et al. A case-control study of gastric cancer and diet in Italy. Int. J. Cancer 1989, 44, 611–616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lunet, N.; Valbuena, C.; Vieira, A.L.; Lopes, C.; Lopes, C.; David, L.; Carneiro, F.; Barros, H. Fruit and vegetable consumption and gastric cancer by location and histological type: Case-control and meta-analysis. Eur. J. Cancer Prev. 2007, 16, 312–327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Castaño-Vinyals, G.; Aragonés, N.; Pérez-Gómez, B.; Martín, V.; Llorca, J.; Moreno, V.; Altzibar, J.M.; Ardanaz, E.; de Sanjosé, S.; Jiménez-Moleón, J.J.; et al. Population-based multicase-control study in common tumors in Spain (MCC-Spain): Rationale and study design. Gac. Sanit. 2015, 29, 308–315. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Santibañez, M.; Alguacil, J.; de la Hera, M.G.; Navarrete-Muñoz, E.M.; Llorca, J.; Aragonés, N.; Kauppinen, T.; Vioque, J.; PANESOES Study Group. Occupational exposures and risk of stomach cancer by histological type. Occup. Environ. Med. 2012, 69, 268–275. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lagiou, P.; Samoli, E.; Lagiou, A.; Peterson, J.; Tzonou, A.; Dwyer, J.; Trichopoulos, D. Flavonoids, vitamin C and adenocarcinoma of the stomach. Cancer Causes Control 2004, 15, 67–72. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Machida-Montani, A.; Sasazuki, S.; Inoue, M.; Natsukawa, S.; Shaura, K.; Koizumi, Y.; Kasuga, Y.; Hanaoka, T.; Tsugane, S. Association of Helicobacter pylori infection and environmental factors in non-cardia gastric cancer in Japan. Gastric. Cancer 2004, 7, 46–53. [Google Scholar] [CrossRef] [Scilit]
- Zaridze, D.; Borisova, E.; Maximovitch, D.; Chkhikvadze, V. Aspirin protects against gastric cancer: Results of a case-control study from Moscow, Russia. Int. J. Cancer 1999, 82, 473–476. [Google Scholar] [CrossRef] [Scilit]
- Hernández-Ramírez, R.U.; Galván-Portillo, M.V.; Ward, M.H.; Agudo, A.; González, C.A.; Oñate-Ocaña, L.F.; Herrera-Goepfert, R.; Palma-Coca, O.; López-Carrillo, L. Dietary intake of polyphenols, nitrate and nitrite and gastric cancer risk in Mexico City. Int. J. Cancer 2009, 125, 1424–1430. [Google Scholar] [CrossRef] [Scilit]
- López-Carrillo, L.; Hernández Avila, M.; Dubrow, R. Chili pepper consumption and gastric cancer in Mexico: A case-control study. Am. J. Epidemiol. 1994, 139, 263–271. [Google Scholar] [CrossRef] [Scilit]
- López-Carrillo, L.; López-Cervantes, M.; Robles-Díaz, G.; Ramírez-Espitia, A.; Mohar-Betancourt, A.; Meneses-García, A.; López-Vidal, Y.; Blair, A. Capsaicin consumption, Helicobacter pylori positivity and gastric cancer in Mexico. Int. J. Cancer 2003, 106, 277–282. [Google Scholar] [CrossRef] [Scilit]
- Zhang, Z.F.; Kurtz, R.C.; Klimstra, D.S.; Yu, G.P.; Sun, M.; Harlap, S.; Marshall, J.R. Helicobacter pylori infection on the risk of stomach cancer and chronic atrophic gastritis. Cancer Detect. Prev. 1999, 23, 357–367. [Google Scholar] [CrossRef] [Scilit]
- Schatzkin, A.; Subar, A.F.; Thompson, F.E.; Harlan, L.C.; Tangrea, J.; Hollenbeck, A.R.; Hurwitz, P.E.; Coyle, L.; Schussler, N.; Michaud, D.S.; et al. Design and serendipity in establishing a large cohort with wide dietary intake distributions: The National Institutes of Health-American Association of Retired Persons Diet and Health Study. Am. J. Epidemiol. 2001, 154, 1119–1125. [Google Scholar] [CrossRef] [Scilit]
- Peres, S.V.; Silva, D.R.M.; Coimbra, F.J.F.; Fagundes, M.A.; Auzier, J.J.N.; Pelosof, A.G.; Araujo, M.S.; Assumpção, P.P.; Curado, M.P. Consumption of processed and ultra-processed foods by patients with stomach adenocarcinoma: A multicentric case-control study in the Amazon and southeast regions of Brazil. Cancer Causes Control. 2022, 33, 889–898. [Google Scholar] [CrossRef] [Scilit]
- DerSimonian, R.; Laird, N. Meta-Analysis in Clinical Trial Control Clin Trials. Control Clin. Trials 1986, 7, 177–188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- StataCorp. Stata Statistical Software: Release 16; StataCorp LLC: College Station, TX, USA, 2019. [Google Scholar]
- Fisberg, M.; Machado, R. History of yogurt and current patterns of consumption. Nutr. Rev. 2015, 73 (Suppl. 1), 4–7. [Google Scholar] [CrossRef] [Scilit]
- Ritchie, M.L.; Romanuk, T.N. A meta-analysis of probiotic efficacy for gastrointestinal diseases. PLoS ONE 2012, 7, e34938. [Google Scholar] [CrossRef] [Scilit]
- Srinarong, C.; Siramolpiwat, S.; Wongcha-um, A.; Mahachai, V.; Vilaichone, R.K. Improved eradication rate of standard triple therapy by adding bismuth and probiotic supplement for Helicobacter pylori treatment in Thailand. Asian Pac. J. Cancer Prev. 2014, 15, 9909–9913. [Google Scholar] [CrossRef] [Scilit]
- Westerik, N.; Reid, G.; Sybesma, W.; Kort, R. The Probiotic Lactobacillus rhamnosus for Alleviation of Helicobacter pylori-Associated Gastric Pathology in East Africa. Front. Microbiol. 2018, 9, 1873. [Google Scholar] [CrossRef] [Scilit]
- Shi, X.; Zhang, J.; Mo, L.; Shi, J.; Qin, M.; Huang, X. Efficacy and safety of probiotics in eradicating Helicobacter pylori: A network meta-analysis. Medicine 2019, 98, e15180. [Google Scholar] [CrossRef] [Scilit]
- Wang, X.; Shu, X.; Li, Q.; Li, Y.; Chen, Z.; Wang, Y.; Pu, K.; Zheng, Y.; Ye, Y.; Liu, M.; et al. Prevalence and risk factors of Helicobacter pylori infection in Wuwei, a high-risk area for gastric cancer in northwest China: An all-ages population-based cross-sectional study. Helicobacter 2021, 26, e12810. [Google Scholar] [CrossRef] [Scilit]
- Scourboutakos, M.J.; Franco-Arellano, B.; Murphy, S.A.; Norsen, S.; Comelli, E.M.; L’Abbé, M.R. Mismatch between Probiotic Benefits in Trials versus Food Products. Nutrients 2017, 9, 400. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Soni, R.; Jain, N.K.; Shah, V.; Soni, J.; Suthar, D.; Gohel, P. Development of probiotic yogurt: Effect of strain combination on nutritional, rheological, organoleptic and probiotic properties. J. Food Sci. Technol. 2020, 57, 2038–2050. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nagaoka, S. Yogurt Production. Methods Mol. Biol. 2019, 1887, 45–54. [Google Scholar]
- Ashraf, R.; Shah, N.P. Selective and differential enumerations of Lactobacillus delbrueckii subsp. bulgaricus, Streptococcus thermophilus, Lactobacillus acidophilus, Lactobacillus casei and Bifidobacterium spp. in yoghurt—A review. Int. J. Food Microbiol. 2011, 149, 194–208. [Google Scholar] [CrossRef] [Scilit]
- Thorning, T.K.; Bertram, H.C.; Bonjour, J.P.; de Groot, L.; Dupont, D.; Feeney, E.; Ipsen, R.; Lecerf, J.M.; Mackie, A.; McKinley, M.C.; et al. Whole dairy matrix or single nutrients in assessment of health effects: Current evidence and knowledge gaps. Am. J. Clin. Nutr. 2017, 105, 1033–1045. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, Y.; Shan, Z.; Ren, H.; Chen, W. Dairy consumption and gastric cancer risk: A meta-analysis of epidemiological studies. Nutr. Cancer 2015, 67, 555–568. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Song, J.W.; Chung, K.C. Observational studies: Cohort and case-control studies. Plast Reconstr Surg. 2010, 126, 2234–2242. [Google Scholar] [CrossRef] [Scilit]
- Jacobs, D.R. Challenges in Research in Nutritional Epidemiology. In Nutritional Health. Nutrition and Health; Temple, N., Wilson, T., Jacobs, D., Jr., Eds.; Humana Press: Totowa, NJ, USA, 2012. [Google Scholar]
- Thornton, K.; Villamor, E. Nutritional Epidemiology. In Encyclopedia of Food and Health; Caballero, B., Finglas, P.M., Toldrá, F., Eds.; Academic Press: Oxford, UK, 2016; pp. 104–107. [Google Scholar]
- Honda, M.; Wong, S.L.; Healy, M.A.; Nakajima, T.; Watanabe, M.; Fukuma, S.; Fukuhara, S.; Ayanian, J.Z. Long-term Trends in Primary Sites of Gastric Adenocarcinoma in Japan and the United States. J. Cancer 2017, 8, 1935–1942. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2023 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).