


Abstract
The most representative indicator of vitamin D status in clinical practice is 25(OH)D3, but new biomarkers could improve the assessment of vitamin D status and metabolism. The objective of this study is to investigate the association of serum vitamin D metabolites and vitamin D metabolite ratios (VMRs) with potentially influential factors in premenopausal women. This is a cross-sectional study based on 1422 women, aged 39–50, recruited from a Madrid Medical Diagnostic Center. Participants answered an epidemiological and a food frequency questionnaire. Serum vitamin D metabolites were determined using an SPE–LC–MS/MS platform. The association between participant’s characteristics, vitamin D metabolites, and VMRs was quantified by multiple linear regression models. Mean 25(OH)D3 concentration was 49.2 + 18.9 nmol/L, with greater deficits among obese, nulliparous, dark-skinned women, and with less sun exposure. A lower R2 ratio (1,25(OH)2D3/25(OH)D3) and a higher R4 (24,25(OH)2D3/1,25(OH)2D3) were observed in nulliparous women, with high sun exposure, and those with low caloric intake or high consumption of calcium, vitamin D supplements, or alcohol. Nulliparous women had lower R1 (25(OH)D3/Vit D3) and R3 (24,25(OH)2D3/25(OH)D3), and older women showed lower R3 and R4. Vitamin D status modified the association of the VMRs with seasons. VMRs can be complementary indicators of vitamin D status and its endogenous metabolism, and reveal the influence of certain individual characteristics on the expression of hydroxylase enzymes.
1. Introduction
Vitamin D has been recently hypothesized as a potentially modifiable factor that could reduce the risk of several diseases, such as cardiovascular diseases, diabetes mellitus, multiple sclerosis [1], mental and autoimmune disorders [2], or some types of neoplasms (such as breast cancer) [3]. The US Endocrine Society considers vitamin D sufficiency when serum levels exceed 75 nmol/L [4], and the Institute of Medicine set up a cutoff of 50 nmol/L [5]. According to the last threshold, vitamin D deficiency (<50 nmol/L) has been estimated to affect around 40% of the European [6] and Spanish [7] population.
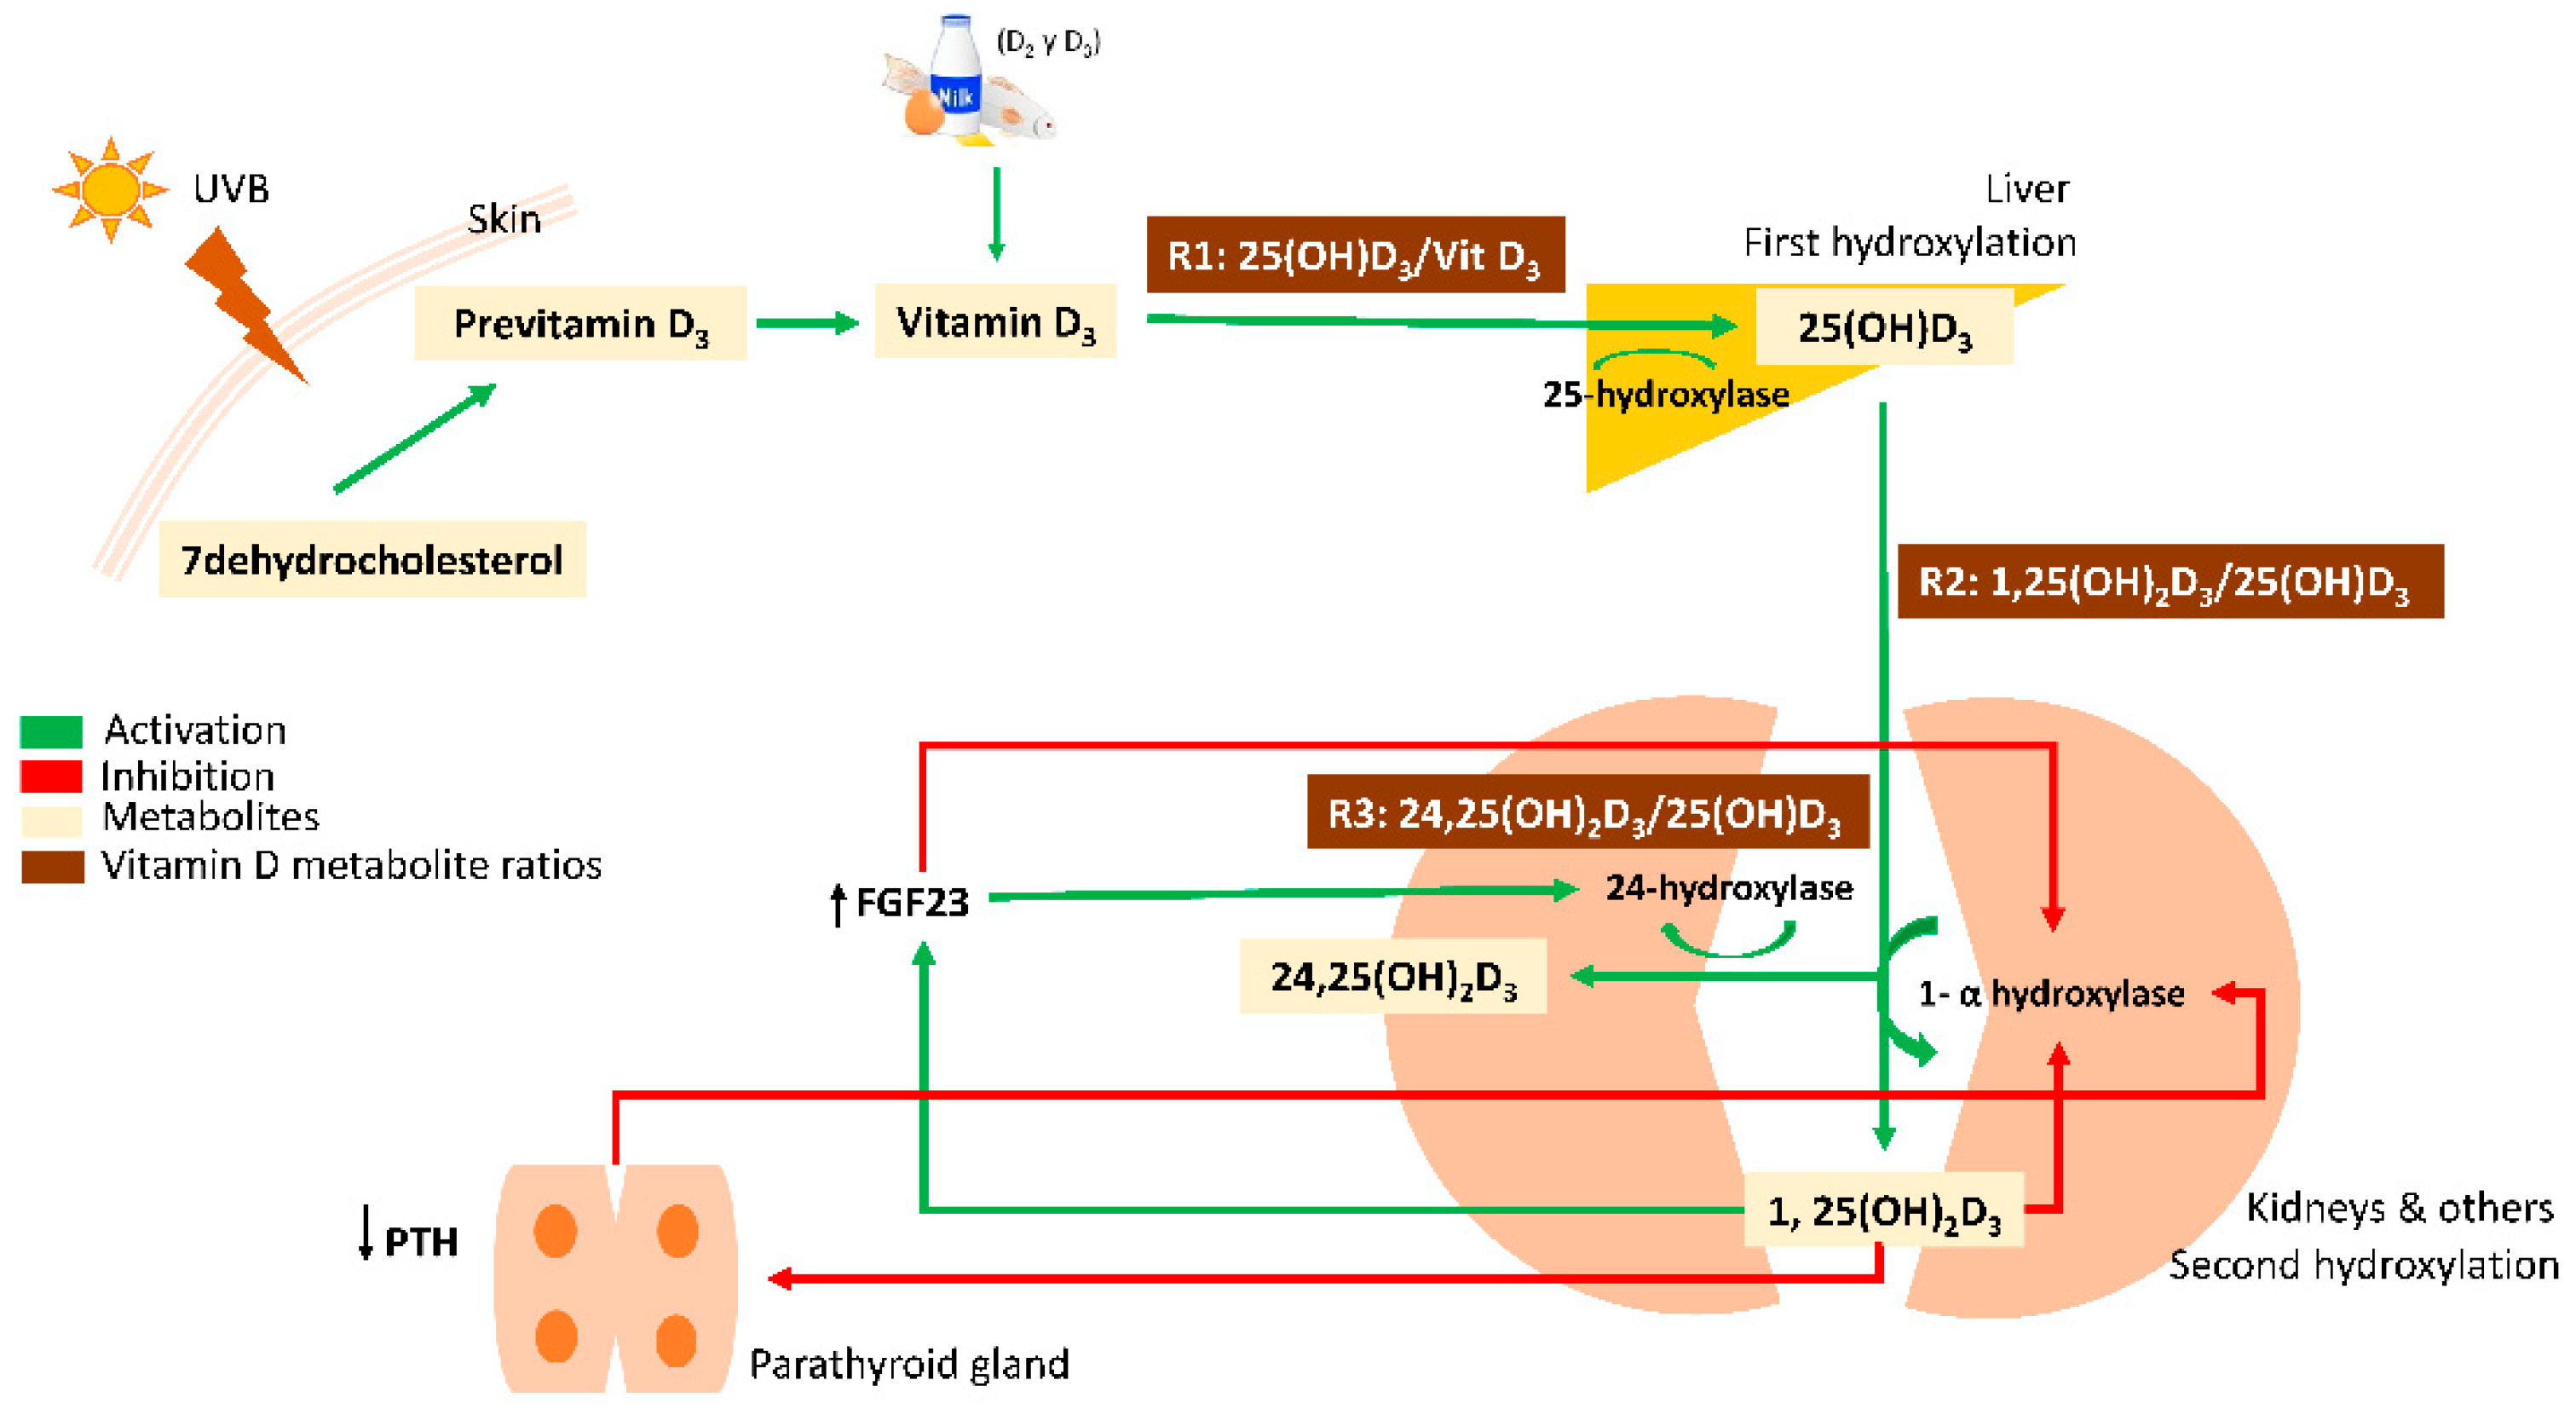
Vitamin D (calciferol) is mainly produced in the skin by the action of ultraviolet B (UVB) radiation from sunlight, which transforms 7-dehydrocholesterol into previtamin D3. This metabolite is considered biologically inactive until it undergoes two enzymatic hydroxylations: the first one in the liver, where previtamin D3 is hydroxylated by the 25-hydroxylase (CYP2R1) to form 25-hydroxyvitamin D3 (25(OH)D3), and then in the kidney, where 25(OH)D3 is converted to the biologically active hormone calcitriol or 1,25-dihydroxyvitamin D3 (1,25(OH)2D3). This second hydroxylation is mediated by 1α-hydroxylase (CYP27B1), which is expressed mainly in the kidney, but also in extra-renal tissues such as breast cells, skin (keratinocytes), immune cells, and bone [4,8]. Vitamin D catabolism takes place in the kidney, where the 24-hydroxylase enzyme (CYP24A1) metabolizes 25(OH)D3 to 24,25-dihydroxyvitamin D3 (24,25(OH)2D3), the main catabolic metabolite with some biological activity [9]. The crucial control point in vitamin D homeostasis is the renal production of 1,25(OH)2D3 via 1α-hydroxylase. Calcitriol (1,25(OH)2D3) can decrease its own production acting directly on the expression of the 1α-hydroxylase or indirectly decreasing parathyroid hormone (PTH) synthesis and, therefore, decreasing 1α-hydroxylase transcription. Rising concentrations of 1,25(OH)2D3 also increase the expression of the phosphaturic factor, fibroblast growth factor 23 (FGF23), which suppresses the expression of 1α-hydroxylase in the kidney and causes up-regulation of CYP24A1 expression [9] (Figure 1).
Figure 1.
Vitamin D metabolism. Previtamin D3 synthesis takes place in the skin by the action of UVB radiation. It undergoes a first hydroxylation in the liver by the enzyme 25-hydroxylase (CYP2R1), forming 25(OH)D3. Subsequently, 25(OH)D3 is hydroxylated to the bioactive 1,25(OH)2D3 by the enzyme 1α-hydroxylase (CYP27B1), predominantly in the kidneys. Vitamin D catabolism is mainly driven by the enzyme 24-hydroxylase (CYP24A1), which metabolizes 25(OH)D3 to 24,25(OH)2D3. Vitamin D homeostasis depends on 1,25(OH)2D3 concentration, which can decrease its own production by directly inhibiting the expression of 1α-hydroxylase or indirectly, by decreasing the synthesis of the parathyroid hormone (↓PTH) or increasing the expression of the phosphaturic factor, fibroblast growth factor 23 (↑FGF23). VMR: Vitamin D Metabolite Ratio.
The most abundant circulating vitamin D metabolite is 25(OH)D3. Despite not being the biologically active form, it has been the most widely used indicator of vitamin D in most epidemiological studies, due in part to the lack of selective and sensitive methods for the determination of dihydroxymetabolites [10]. Despite its clinical relevance, the determination of vitamin D3 metabolites continues to be a challenge, as it provides a more complete snapshot of vitamin D3 status due to its physical and chemical properties (hydrophobic nature, thermal and UV instability, and similar structure). In addition, several limitations hinder the utility of 25(OH)D3 in clinical practice, such as analytical aspects and interpretation of results [9]. In response to these limitations, new candidate biomarkers have been postulated that could improve the assessment of vitamin D status and metabolism [9]. Among these emerging candidates, vitamin D metabolite ratios (VMRs) are beginning to be used in recent studies [10,11,12,13,14,15,16], since they are not affected by the concentration of vitamin D binding proteins, are good indicators of the expression of hydroxylase enzymes, and could be useful to provide a better assessment of vitamin D status [17].
This study sought to evaluate potentially influential factors in serum levels of vitamin D3, 25(OH)D3, 1,25(OH)2D3, 24,25(OH)2D3, and the four VMRs directly connected by a substrate/product relationship (25(OH)D3/VitD3, 1,25(OH)2D3/25(OH)D3, 24,25(OH)2D3/25(OH)D3, and 24,25(OH)2D3/1,25(OH)2D3) in middle-aged women close to menopause, a period with higher risk of developing vitamin D deficiency [18]. The knowledge of the vitamin D status and its metabolism in this group of women, as well as the sociodemographic factors and lifestyles that are associated, is of great interest to prevent or mitigate bone loss and other conditions related to both menopause and vitamin D deficiency.
2. Materials and Methods
2.1. Study Population
Between June 2013 and May 2015, 1466 premenopausal women, aged 39 to 50, who worked at the Madrid City Council, were invited to participate in the DDM-Madrid study, aimed to assess the effect of vitamin D on mammographic density. These women were recruited in the Madrid Medical Diagnostic Center (Madrid Salud), where they attended to undergo their routine gynecological check-up. Participants were excluded if they were postmenopausal (at least 1 year without menstruation); were pregnant or breastfeeding; had breast cancer; or had undergone a mastectomy, breast reconstruction, or breast augmentation.
2.2. Recruitment and Data Collection
Women were invited to participate in the study by phone, when the selection criteria were verified. Overall participation rate was 88%. The day that each participating woman had her medical examination scheduled, the interviewers administered a standardized epidemiological questionnaire, drew a blood sample, and took anthropometric measurements (height, weight, and waist and hip circumference). The questionnaire collected sociodemographic variables, information on childhood and youth, personal and family medical history, gynecological and obstetric history, work history, skin type and sunbathing habits, sleep habits, tobacco and alcohol consumption, and physical activity. Participants also completed a validated [19] 117-item semi-quantitative food frequency questionnaire that included eating habits during the previous 12 months. Blood samples were centrifuged, aliquoted, and stored at −80 °C in the Carlos III Institute of Health Biobank. The DDM-Madrid study was conducted in accordance with the Declaration of Helsinki guidelines. All participants signed an informed consent, and the protocol was approved by the Ethics and Animal Welfare Committee of the Carlos III Institute of Health. Further details regarding the study design have been previously published [20,21].
2.3. Biochemical Analyses
The determination of vitamin D metabolites was carried out in the Metabolomics Unit of the University of Córdoba using an automatic solid-phase extraction unit on-line connected to a liquid chromatograph–tandem mass spectrometer arrangement (SPE-LC-MS/MS). This method was validated by a standard reference material, applying the Vitamin D Standardization Program (VDSP) protocols [22], and according to external quality assurance scheme (DEQAS) [23]. Briefly, 200 µL of filtered serum spiked with deuterated standards of the analytes was introduced for cleanup–chromatographic separation as required tandem mass spectrometry detection. Calibration curves for quantification were obtained using the ratio between the chromatographic peak area of each analyte and that of the corresponding deuterated standard. More information on sample preparation and LC-MS/MS analysis can be found in the article by Mena-Bravo et al. [24], and in Appendix A.
2.4. Statistical Methods
After excluding 27 women whose serum vitamin D levels could not be measured, and 17 women with lack of information in key covariates, the final sample size included 1422 participants.
Descriptive characteristics of participants were summarized as absolute values and percentages. Geometric means (GM), and the 25th, 50th, and 75th percentiles of Vit D3, 25(OH)D3, 1,25(OH)2D3, and 24,25(OH)2D3, according to women characteristics were also described. Comparisons were also made using the Wald test, with linear regression models adjusted for the weekly sun exposure score, vitamin D intake, and season. The weekly sun exposure score was calculated, taking into account the daily time in sun and the skin area exposed, according to the study by Hanwell et al. [25]. GM of the following VMRs were also calculated: R1: 25(OH)D3/Vit D3; R2: 1,25(OH)2D3/25(OH)D3; R3: 24,25(OH)2D3/25(OH)D3; and R4: 24,25(OH)2D3/1,25(OH)2D3.
Since the distribution of metabolite and VMR concentrations were positively skewed, the values were log-transformed to improve normality. To assess their association with women characteristics, we estimated geometric mean ratios (GMR) and 95% confidence intervals through multiple linear regression models, adjusted for weekly sun exposure score, vitamin D intake and season, and for those variables that were associated with each metabolite’s concentration (p < 0.10) in the above-described Wald test analysis. For VMRs, models were adjusted for the same 3 mentioned variables plus those variables that, in this last analysis, showed to be relevant for any of the two metabolites of each ratio (p < 0.05). Differences in the associations of VMR according to vitamin D status (deficiency: 25(OH)D3 < 50 nmol/L and non-deficiency: 25(OH)D3 > 50 nmol/L) were also explored. Possible effect modifications were tested using the likelihood ratio test. Finally, to take into account the problem of multiple comparisons or multiple testing, p-values were also suitably adjusted by controlling the expected proportion of false positives, as proposed by Benjamini and Hochberg [26]. All analyses were performed using STATA/MP 14.0 software.
3. Results
The mean age of the participants was 44 years. As can be seen in Table 1, 23% of the women were overweight, and almost 10% were obese. Most were university graduates (61%). The percentage of nulliparous, non-smoking, abstemious, and sedentary women was 24%, 39%, 20%, and 42%, respectively. Hypercholesterolemia was reported in 13% of the women, and 10% were in treatment with corticosteroids. Most of the participants had a type IV skin phototype. The mean (+standard deviation) consumption of calories and calcium was 1976 + 681 Kcal/day and 1129 + 491 mg/day, respectively. Sun exposure, according to the weekly sun exposure score, was low in 47% of women, and vitamin D intake was lower than 5 µg/day in 72%. Most of the samples were obtained in spring (33%) and fall (29%).
Table 1.
Characteristics of the participants and distribution of vitamin D metabolite levels according to them.
The mean 25(OH)D3 concentration was 49.2 + 18.9 nmol/L. More than half of the participants (59%) had vitamin D deficiency (25(OH)D3 < 50 nmol/L). Serum levels were significantly higher in women with adequate body mass index (BMI), with one or two children, with higher sun exposure, in the most physically active women, in those taking vitamin D supplements, and in samples collected during the summer months. Both native vitamin D and 24,25(OH)2D3 showed the same pattern as 25(OH)D3 regarding BMI, physical activity, sun exposure, and season. 24,25(OH)2D3 levels were also lower in nulliparous and in current smokers, were inversely associated with age, and positively associated with calcium and vitamin D intake. Vitamin D3 levels were also higher in corticosteroid users. Finally, 1,25(OH)2D3 levels were higher in nulliparous women with higher calorie intake and in samples obtained in winter (Table 1).
Table 2 shows the association between the concentrations of vitamin D metabolites and women’s characteristics. Obese women had lower levels of Vit D3, 25(OH)D3 and 24,25(OH)2D3, while physically active women had higher concentrations of these metabolites. Parous women, as well as those taking vitamin D supplements, had higher concentrations of 25(OH)D3 and 24,25(OH)2D3. Sun exposure was positively associated with Vit D3, 25(OH)D3, and 24,25(OH)2D3 levels. Concentrations of these three metabolites were also higher in samples obtained in summer, and lower in the samples collected in winter. Women using corticosteroids had higher Vit D3 concentrations (GMR = 1.09; 95%CI = 1.01–1.17). Current smokers presented lower levels of 24,25(OH)2D3 (GMR = 0.93; 95%CI = 0.87–0.99). Phototype V-VI was associated with decreased 25(OH)D3 concentrations (GMR = 0.90; 95%CI = 0.83–0.99). Finally, participants with higher calcium intake and lower calorie consumption had lower levels of 1,25(OH)2D3.
Table 2.
Association between vitamin D metabolite concentrations and characteristics of women.
With respect to VMR, older women presented lower values of R3 (GMR > 45 years = 0.94; 95%CI = 0.90–0.98) and R4 (GMR>45 years = 0.92; 95%CI = 0.88–0.97). Nulliparous women presented lower values of R1 (GMR = 0.92; 95%CI = 0.85–0.99), R3 (GMR = 0.95; 95%CI = 0.91–1.00), and R4 (GMR = 0.84; 95%CI = 0.79–0.90), but higher values of R2 (GMR = 1.13; 95%CI = 1.06–1.19). This last ratio presented an inverse association with alcohol consumption (GMR>10g/day = 0.90; 95%CI = 0.83–0.98). Physically active women had higher R4 values (GMR>12 MET-h/week = 1.09; 95%CI = 1.02–1.16), while current smokers had lower values of this ratio. While R2 was inversely associated with sun exposure (GMRWSES=29–56 = 0.82; 95%CI = 0.76–0.89) and calcium intake (GMR>1246.9 mg/day = 0.91; 95%CI = 0.85–0.98), and positively with calorie consumption (GMR>2144.0 kcal/day = 1.13; 95%CI = 1.05–1.22), the association of R4 with these three variables was exactly the opposite. Women who took vitamin D supplements showed higher R1 (GMR = 1.21; 95%CI = 1.08–1.35) and R4 values (GMR = 1.10; 95%CI = 1.01–1.21) and lower R2 values (GMR = 0.86; 95%CI = 0.79–0.93). All ratios showed seasonal variations, with R1 values being higher in fall, R2 values in winter, and R3 and R4 values in summer and fall. In contrast, the lowest levels were obtained in summer for R1, in spring for R2 and R3, and in winter for R4 (Table 3).
Table 3.
Association between vitamin D metabolite ratios and characteristics of women.
Table 4 and Table 5 show the association of VMR with women’s characteristics in participants with deficient (25(OH)D3 < 50 nmol/L) and non-deficient (25(OH)D3 > 50 nmol/L) serum vitamin D levels. For most of the studied associations, no differences were observed between these two groups. However, among participants with vitamin D deficiency, those who were taking corticosteroids had lower values of the R1 ratio than those who did not take corticosteroids, while no statistically significant differences were observed in participants with non-deficient levels of vitamin D (P-het = 0.027). The association of hypercholesterolemia treated with statins with VMR (decreasing the R2 values and increasing the R4 values) was only observed among women with non-deficient serum vitamin D levels. Finally, vitamin D status modified the association of the first three ratios with the season of the year, while R1 was only associated in women with sufficient levels of vitamin D (P-het < 0.001), R2 was altered only in women with deficient levels of this vitamin (P-het = 0.020), and the high R3 value in summer was only observed among participants with non-deficient vitamin D concentrations.
Table 4.
Association between R1 and R2 metabolite ratios and characteristics of women according to vitamin D status.
Table 5.
Association between R3 and R4 metabolite ratios and characteristics of women according to vitamin D status.
4. Discussion
To our knowledge, this is the first study providing information on the association of serum VMRs with several sociodemographic and lifestyle-related characteristics in premenopausal women. Our results show a notable vitamin D deficiency in the participating women, as well as the influence of certain factors (such as age, parity, and several lifestyles) on the vitamin D serum levels, its metabolites, and VMR.
Vitamin D deficiency (<50 nmol/L of 25(OH)D3) is a global problem [4] that affects around 40% of the European population [6,27], and the Southern European countries [7]. In Spain, despite abundant sunshine, it has been estimated that 40% of the Spanish adult population have serum concentrations of 25(OH)D3 below 50 nmol/L, and 18% below 25 nmol/L. These figures are 35% and 27% when we refer exclusively to the elderly population and postmenopausal women [7]. In our study, more than half (59%) of the participants had deficient levels of vitamin D, and only 9% had optimal levels (>75 nmol/L). Nulliparous women, and those with obesity or with darker skin, presented lower levels of 25(OH)D3, while women with greater sun exposure, those who took vitamin D supplements, were physically active, drank more alcohol, and those whose samples were collected in summer had higher concentrations. Regarding BMI, our results are in line with other Spanish [28] and international studies [29,30], in which obesity was significantly associated with lower 25(OH)D3 levels. Circulating vitamin D concentrations are partially determined by genetic factors, and play an important role in the process of adipogenesis and inflammation status in adipocytes and adipose tissue [31]. Due to its fat solubility, vitamin D is retained by the body fat mass, resulting in lower availability of vitamin D for metabolic function in obese people [31,32]. Regarding parity, although a recent study has shown no association [33], Andersen et al. observed that the prevalence of vitamin D insufficiency was less frequent in nulliparous women [34]. The lower levels detected in our nulliparous participants could be due to lifestyles that imply less sun exposure or greater protection from the sun, different eating habits (egg and dairy products consumption was significantly lower in nulliparous participants), or the involvement of endogenous factors (such as the influence of hormones on vitamin D metabolism). Several observational studies have shown that vitamin D deficiency is a risk marker for reduced female fertility and various adverse pregnancy outcomes [35,36]. Leisure-time physical activity appears to be an effective manner of maintaining adequate vitamin D concentrations [37]. Such association has often been attributed to confounding factors, but recent studies indicate that exercise may have a direct and causal effect on vitamin D status, possibly through the mobilization of adipose-derived vitamin D and/or 25(OH)D3 [38], or through an increase in muscle use producing the release of 25OHD from its interior [39]. The association between alcohol consumption and vitamin D serum levels remains controversial, although recent studies, with large sample sizes, showed positive associations [40]. Consistent with our findings, other factors related to sun exposure, such as short time spent in the sun, low amount of skin surface exposed, samples collected in winter/early spring, and increased skin pigmentation have been associated with higher risk of 25(OH)D3 deficiency in the literature [41]. Finally, and as expected, the intake of vitamin D supplements increased serum levels of 25(OH)D3. However, the intake of these supplements is very infrequent, both among the women of our study and in Spain in general [42]. Only 19% of our participants took the 5 µg/day of vitamin D recommended by the Spanish Federation of Societies of Nutrition, Food, and Dietetics (FESNAD) in 2010 [43], and only 0.4% took the 15 µg/day recommended in 2019 by the European Food Safety Authority (EFSA) for the adult population [44].
Although 25(OH)D3 is still recommended as the marker of choice by current guidelines from scientific organizations, growing evidence indicates significant limitations that hamper the utility of this analyte in clinical practice, including analytical aspects and interpretation of results [9]. VMRs are promising emerging biomarkers that may provide additional information in assessing vitamin D status [9,45]. The first ratio (25(OH)D3/Vit D3), represents the activity of 25-hydroxylase enzyme in the liver, which is the main enzyme responsible for the conversion of vitamin D3 to the main circulating form of this vitamin, the 25(OH)D3. The values of this ratio were similar to those described in the study by Mena-Bravo et al. [10]. This ratio was higher in women taking supplements and among participants with sufficient 25(OH)D3 levels whose samples were collected in fall or winter, and lower among nulliparous women and corticosteroid users with deficient vitamin D levels.
The second ratio (1,25(OH)2D3/25(OH)D3) represents the 1α-hydroxylase activity, an enzyme encoded by the CYP27B1 gene in the kidney, where 25(OH)D3 is converted to the active 1,25(OH)2D3. We found a higher ratio in obese women (mainly in those with deficient serum vitamin D levels), in nulliparous women, in those with more caloric diets, and in women with deficient vitamin D concentrations whose samples were collected in winter. On the contrary, this ratio was lower in women with higher consumption of alcohol, calcium, vitamin D supplements, and statin users; in women with greater sun exposure; and in samples collected in spring and summer (both results only detected in women with vitamin D deficiency). The values of this ratio in our participants are slightly higher than those described by Mena-Bravo et al. [10] (average ± SD: 0.0029 ± 0.002) and, although we have not found studies reporting characteristics associated with this ratio, there is evidence that high dietary calcium intake reduces 1α-hydroxylase activity (reflected in a lower R2 ratio), while low calcium intake down-regulates 24-hydroxylase expression [9,46].
The third ratio (24,25(OH)2D3/25(OH)D3) is mediated by the CYP24A1 gene that encodes the enzyme 24-hydroxylase, which catalyzes the conversion of 25(OH)D3 into 24,25(OH)2D3. When sufficient amounts of biologically active vitamin D are available, CYP24A1 is up-regulated and more 24,25(OH)2D3 is formed [9]. This ratio may be of potential use as an indicator of vitamin D deficiency and as a predictor of the change in 25(OH)D3 after vitamin D supplementation. It may also help explain some of the inter-individual differences in the response of serum 25(OH)D3 to the same administered dose of vitamin D [9,13,47,48,49]. In some studies, low levels of this ratio seem to be related to the increasing all-cause mortality in patients with chronic kidney disease and risk of hip fracture in older adults [16,50]. However, in our study, we found no differences in this ratio between the participants that were taking vitamin D supplements and those who did not (regardless their vitamin D status), in line with what was observed in previous studies [14,45], and contrary to what was observed in Tang’s study [11]. Older women, nulliparous women, and those whose samples were collected in spring had a lower R3 ratio, although the association of this ratio with season varied as a function of vitamin D levels. Regarding R3 mean values, two previous studies have described figures that are in line with those obtained in our study [10,11].
Finally, the fourth ratio (24,25(OH)2D3/1,25(OH)2D3) could also be a good indicator of vitamin D status. Tang et al., observed an inverse correlation between the 1,25(OH)2D3/24,25(OH)2D3 ratio and the 25(OH)D3 levels, so that when vitamin D levels were insufficient, the production of 1,25(OH)2D3 was favored to the detriment of its conversion to 24,25(OH)2D3 [11]. This phenomenon is also compatible with our results, since the GM of R4 was lower in women with vitamin D deficiency than in those with non-deficient levels. The R4 ratio was higher in women who consumed calcium and vitamin D supplements, in participants with high sun exposure, in those who were physically active and in samples collected in summer and fall. On the contrary, the oldest women, nulliparous women, those whose samples were collected in winter or spring, and the participants with non-deficient levels of vitamin D who consumed many calories had a lower R4 ratio.
The cross-sectional design of this study limits the possibility of establishing a temporal relationship between the exposures and vitamin D metabolite levels. This sample includes only premenopausal women recruited from a single center, so the results cannot be extrapolated to the general population. In addition, only a single blood sample was collected at the beginning of the study, so the participants’ usual vitamin D status may not have been adequately reflected. On the other hand, given that we have used a novel approach to provide a more complete picture of vitamin D3 metabolism, the results of this study should be considered as hypothesis-generating and should be viewed with caution. Precisely, due to its hypothesis-generating approach and the exploratory nature of the study, corrections for multiple testing were not applied in the main analyses [51], although results adjusted using the Benjamini and Hochberg method [26] are reported in the Supplementary Material (Tables S1 and S2). Finally, even though we have included the main variables described in the literature as associated with vitamin D levels in our models, the possibility of residual confounding cannot be ruled out.
The greatest strength of our study is its novelty. In a relatively large sample of participants, we were able to quantify vitamin D metabolites, the ratios between them, and the factors that contribute to explain metabolic variations. In addition, SPE-LC-MS/MS is a sensitive automated method for the analysis of serum vitamin D and metabolites that provides reliable and robust results. This method was validated by a standard reference material and according to DEQAS [23].
5. Conclusions
In general, vitamin D metabolite profile in nulliparous women and older women was compatible with lower activity of the enzyme 24-hydroxylase, which catabolizes 25(OH)2D3 to 24,25(OH)2D3. Furthermore, nulliparous women and those who consumed more calories showed an increase in calcitriol levels to the detriment of the concentrations of the other two metabolites. The opposite was observed among the participants with greater consumption of calcium, alcohol, or with greater sun exposure. Finally, the association of VMR with seasons was different depending on vitamin D status. These results highlight the added value of VMR as complementary indicators of vitamin D status and its endogenous metabolism, being considered better predictors of vitamin D treatment response and clinically important outcomes. The results also reveal the potential contribution of certain factors in the greater or lesser expression/activity of hydroxylase enzymes.
Supplementary Materials
The following are available online at https://www.mdpi.com/article/10.3390/nu13113747/s1, Table S1: Association between vitamin D metabolite concentrations and characteristics of women. Analysis adjusted for multiple testing. Table S2: Association between vitamin D metabolite ratios and characteristics of women. Analysis adjusted for multiple testing.
Author Contributions
M.J.T., data curation, formal analysis, investigation, methodology, writing—original draft; F.P.-C., investigation, methodology, resources, writing—review & editing; B.P.-G., investigation, methodology, writing—review & editing; N.F.d.L.-B., investigation, methodology, writing—review & editing; E.R.-M., investigation, methodology, writing—review & editing; A.C., investigation, methodology, writing—review & editing; P.L., data curation, resources, writing—review & editing; M.Á.S., data curation, resources, writing—review & editing; M.N.P., resources, writing—review & editing; M.M.-C., resources, writing—review & editing; M.D.L.d.C., investigation, methodology, resources, writing—review & editing; V.L., conceptualization, methodology, formal analysis, investigation, supervision, writing—original draft, writingreview & editing; M.P., conceptualization, methodology, funding acquisition, investigation, supervision, project administration, writing—review & editing. All authors have read and agreed to the published version of the manuscript.
Funding
This study was funded by the Spanish Ministry of Health (EC11–273) and by the Carlos III Institute of Health (PI15CIII/0029). The article presents independent research. The views expressed are those of the authors and not necessarily those of the Carlos III Institute of Health.
Institutional Review Board Statement
The study was conducted according to the guidelines of the Declaration of Helsinki, and approved by the Ethics and Animal Welfare Committee of the Carlos III Institute of Health.
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
Some or all datasets generated during and/or analyzed during the current study are not publicly available but are available from the corresponding author on reasonable request.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Appendix A.1. Sample Preparation
A serum aliquot of 240 µL was poured in an amber glass vial and spiked with 10 μL of the deuterated working solution—giving the following final concentrations: 25, 25, 5 and 0.3 ng mL−1 of vitamin D3-d3, 25(OH)D3-d3, 24,25(OH)2D3-d6 and 1,25(OH)2D3-d6, respectively—, shaken and located into the autosampler. The sample loop was filled with 0.2 mL from the sample vial, which was refrigerated in the autosampler at 6 °C. Shortly, the protocol starts by activation of the SPE sorbent with methanol, followed by a conditioning and equilibration step with 25:75 (V/V) ACN–water acidified with 0.7% (V/V) formic acid, the same solution used for sample loading into the cartridge. Under these conditions, the target compounds are retained in the cartridge, which is washed with 30:70 (V/V) ACN–water to remove retained mid-polar interferents. Then, the chromatographic step starts by switching the left clamp valve of the SPE automated station and putting the cartridge into contact with the initial mobile phase, which also acts as eluent. Elution of the target analytes takes 5 min (longer elution times favor elution of non-polar interferents, which remain retained in the sorbent within the selected interval).
Appendix A.2. LC–MS/MS Analysis
The initial chromatographic mobile phase was 5 mM ammonium formate in 85:15 (V/V) methanol–water at a flow rate of 0.5 mL min−1. The temperature of the analytical column compartment was set at 15 °C. At min 2, a linear gradient was programmed to obtain a 100% 5 mM ammonium formate in methanol at min 5. The final gradient conditions were maintained for 10 min until the end of the chromatographic separation step. The total analysis time was 15 min, 10 min being required for re-establishing and equilibrating the initial conditions. The chromatographic–detection step of a sample and the SPE step of the next sample overlapped, thus improving the analysis frequency.
The eluate from the chromatographic column was monitored by MS/MS in MRM mode. The flow and temperature of the drying gas (N2) were 9 L min−1 and 350 °C, respectively. The nebulizer pressure was 50 psi, and the capillary voltage 4750 V in the positive ionization mode.
References
- Sridhar, S.B.; Rao, P.G.; Multani, S.K.; Jain, M. Assessment of prevalence of hypovitaminosis D in multiethnic population of the United Arab Emirates. J. Adv. Pharm. Technol. Res. 2016, 7, 48–53. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Smith, G.; Wimalawansa, S.J.; Laillou, A.; Sophonneary, P.; Un, S.; Hong, R.; Poirot, E.; Kuong, K.; Chamnan, C.; Reyes, F.N.D.L.; et al. High Prevalence of Vitamin D Deficiency in Cambodian Women: A Common Deficiency in a Sunny Country. Nutrients 2016, 8, 290. [Google Scholar] [CrossRef] [Scilit]
- Anderson, L.N.; Cotterchio, M.; Kirsh, V.A.; Knight, J.A. Ultraviolet Sunlight Exposure During Adolescence and Adulthood and Breast Cancer Risk: A Population-based Case-Control Study Among Ontario Women. Am. J. Epidemiol. 2011, 174, 293–304. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Holick, M.; Binkley, N.C.; Bischoff-Ferrari, H.; Gordon, C.M.; Hanley, D.A.; Heaney, R.P.; Murad, M.H.; Weaver, C.M. Evaluation, Treatment, and Prevention of Vitamin D Deficiency: An Endocrine Society Clinical Practice Guideline. J. Clin. Endocrinol. Metab. 2011, 96, 1911–1930. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- IOM, Institute of Medicine. Dietary Reference Intakes for Calcium and Vitamin D; National Academies Press: Washington, DC, USA, 2011. [Google Scholar]
- Gaksch, M.; Jorde, R.; Grimnes, G.; Joakimsen, R.M.; Schirmer, H.; Wilsgaard, T.; Mathiesen, E.B.; Njølstad, I.; Løchen, M.-L.; März, W.; et al. Vitamin D and mortality: Individual participant data meta-analysis of standardized 25-hydroxyvitamin D in 26916 individuals from a European consortium. PLoS ONE 2017, 12, e0170791. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manios, Y.; Moschonis, G.; Lambrinou, C.-P.; Tsoutsoulopoulou, K.; Binou, P.; Karachaliou, A.; Breidenassel, C.; Gonzalez-Gross, M.; Kiely, M.; Cashman, K.D. A systematic review of vitamin D status in southern European countries. Eur. J. Nutr. 2018, 57, 2001–2036. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- SACN, Scientific Advisory Committee on Nutrition. Vitamin D and Health. 2016. Available online: https://assets.publishing.service.gov.uk/government/uploads/system/uploads/attachment_data/file/537616/SACN_Vitamin_D_and_Health_report.pdf (accessed on 20 October 2021).
- Herrmann, M.; Farrell, C.-J.L.; Pusceddu, I.; Fabregat-Cabello, N.; Cavalier, E. Assessment of vitamin D status—A changing landscape. Clin. Chem. Lab. Med. 2017, 55, 3–26. [Google Scholar] [CrossRef] [Scilit]
- Mena-Bravo, A.; Calderón-Santiago, M.; Lope, V.; Kogevinas, M.; Pollán, M.; de Castro, M.L.; Priego-Capote, F. Vitamin D3 levels in women and factors contributing to explain metabolic variations. J. Steroid Biochem. Mol. Biol. 2021, 211, 105884. [Google Scholar] [CrossRef] [Scilit]
- Tang, J.C.Y.; Team, B.F.; Jackson, S.; Walsh, N.P.; Greeves, J.; Fraser, W.D.; Ball, N. The dynamic relationships between the active and catabolic vitamin D metabolites, their ratios, and associations with PTH. Sci. Rep. 2019, 9, 6974. [Google Scholar] [CrossRef] [Scilit]
- Ramakrishnan, S.; Steck, S.E.; Arab, L.; Zhang, H.; Bensen, J.T.; Fontham, E.T.H.; Johnson, C.S.; Mohler, J.L.; Smith, G.J.; Su, L.J.; et al. Association among plasma 1, 25 (OH) 2D, ratio of 1, 25 (OH) 2D to 25 (OH) D, and prostate cancer aggressiveness. Prostate 2019, 79, 1117–1124. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dirks, N.F.; Ackermans, M.T.; Lips, P.; De Jongh, R.T.; Vervloet, M.G.; De Jonge, R.; Heijboer, A.C. The When, What & How of Measuring Vitamin D Metabolism in Clinical Medicine. Nutrients 2018, 10, 482. [Google Scholar] [CrossRef] [Scilit]
- Aloia, J.; Fazzari, M.; Shieh, A.; Dhaliwal, R.; Mikhail, M.; Hoofnagle, A.N.; Ragolia, L. The vitamin D metabolite ratio (VMR) as a predictor of functional biomarkers of bone health. Clin. Endocrinol. 2017, 86, 674–679. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Selamet, U.; Katz, R.; Ginsberg, C.; Rifkin, D.E.; Fried, L.F.; Kritchevsky, S.B.; Hoofnagle, A.N.; Bibbins-Domingo, K.; Drew, D.; Harris, T.; et al. Serum calcitriol concentrations and kidney function decline, heart failure, and mortality in elderly community-living adults: The health, aging, and body composition study. Am. J. Kidney Dis. 2018, 72, 419–428. [Google Scholar] [CrossRef] [Scilit]
- Bansal, N.; Katz, R.; Appel, L.; Denburg, M.; Feldman, H.; Go, A.S.; He, J.; Hoofnagle, A.; Isakova, T.; Kestenbaum, B.; et al. Vitamin D Metabolic Ratio and Risks of Death and CKD Progression. Kidney Int. Rep. 2019, 4, 1598–1607. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ginsberg, C.; Hoofnagle, A.N.; Katz, R.; Becker, J.O.; Kritchevsky, S.B.; Shlipak, M.G.; Sarnak, M.J.; Ix, J.H. The Vitamin D Metabolite Ratio Is Independent of Vitamin D Binding Protein Concentration. Clin. Chem. 2021, 67, 385–393. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lerchbaum, E. Vitamin D and menopause—A narrative review. Maturitas 2014, 79, 3–7. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vioque, J.; INMA-Valencia Cohort Study; Navarrete-Muñoz, E.-M.; Gimenez-Monzó, D.; García-De-La-Hera, M.; Granado, F.; Young, I.S.; Ramón, R.; Ballester, F.; Murcia, M.; et al. Reproducibility and validity of a food frequency questionnaire among pregnant women in a Mediterranean area. Nutr. J. 2013, 12, 26. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lope, V.; Toribio, M.J.; Pérez-Gómez, B.; Castelló, A.; Mena-Bravo, A.; Sierra, M.; Lucas, P.; Herrán-Vidaurrázaga, M.D.C.; González-Vizcayno, C.; Pino, M.N.; et al. Serum 25-hydroxyvitamin D and mammographic density in premenopausal Spanish women. J. Steroid Biochem. Mol. Biol. 2019, 189, 101–107. [Google Scholar] [CrossRef] [Scilit]
- Lope, V.; Pozo, M.D.P.D.; Criado-Navarro, I.; Pérez-Gómez, B.; Pastor-Barriuso, R.; Ruiz, E.; Castelló, A.; Lucas, P.; Sierra, Á.; Salas-Trejo, D.; et al. Serum Phospholipid Fatty Acids and Mammographic Density in Premenopausal Women. J. Nutr. 2020, 150, 2419–2428. [Google Scholar] [CrossRef] [Scilit]
- Cashman, K.D.; Dowling, K.G.; Škrabáková, Z.; Kiely, M.; Lamberg-Allardt, C.; Durazo-Arvizu, R.A.; Sempos, C.T.; Koskinen, S.; Lundqvist, A.; Sundvall, J.; et al. Standardizing serum 25-hydroxyvitamin D data from four Nordic population samples using the Vitamin D Standardization Program protocols: Shedding new light on vitamin D status in Nordic individuals. Scand. J. Clin. Lab. Investig. 2015, 75, 549–561. [Google Scholar] [CrossRef] [Scilit]
- Mena-Bravo, A.; Priego-Capote, F.; de Castro, M.L. Two-dimensional liquid chromatography coupled to tandem mass spectrometry for vitamin D metabolite profiling including the C3-epimer-25-monohydroxyvitamin D3. J. Chromatogr. A 2016, 1451, 50–57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bravo, A.M.; Ferreiro-Vera, C.; Priego-Capote, F.; Maestro, M.; Mouriño, A.; Quesada-Gómez, J.; de Castro, M.L. Quantitative analytical method to evaluate the metabolism of vitamin D. Clin. Chim. Acta 2015, 442, 6–12. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hanwell, H.; Vieth, R.; Cole, D.; Scillitani, A.; Modoni, S.G.; Frusciante, V.; Ritrovato, G.; Chiodini, I.; Minisola, S.; Carnevale, V. Sun exposure questionnaire predicts circulating 25-hydroxyvitamin D concentrations in Caucasian hospital workers in southern Italy. J. Steroid Biochem. Mol. Biol. 2010, 121, 334–337. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Benjamini, Y.; Hochberg, Y. Controlling the False Discovery Rate: A Practical and Powerful Approach to Multiple Testing. J. R. Stat. Soc. Ser. B (Stat. Methodol.) 1995, 57, 289–300. [Google Scholar] [CrossRef] [Scilit]
- Cashman, K.D.; Dowling, K.G.; Škrabáková, Z.; Gonzalez-Gross, M.; Valtueña, J.; De Henauw, S.; Moreno, L.; Damsgaard, C.T.; Michaelsen, K.F.; Mølgaard, C.; et al. Vitamin D deficiency in Europe: Pandemic? Am. J. Clin. Nutr. 2016, 103, 1033–1044. [Google Scholar] [CrossRef] [Scilit]
- Rodríguez-Rodríguez, E.; Navia, B.; López-Sobaler, A.M.; Ortega, R.M. Vitamin D in Overweight/Obese Women and Its Relationship With Dietetic and Anthropometric Variables. Obesity 2009, 17, 778–782. [Google Scholar] [CrossRef] [Scilit]
- González, L.; Ramos-Trautmann, G.; Díaz-Luquis, G.M.; Pérez, C.M.; Palacios, C. Vitamin D status is inversely associated with obesity in a clinic-based sample in Puerto Rico. Nutr. Res. 2015, 35, 287–293. [Google Scholar] [CrossRef] [Scilit]
- Pereira-Santos, M.; Costa PR, F.; Assis AM, O.; Santos, C.A.S.T.; Santos, D.B. Obesity and vitamin D deficiency: A systematic review and meta-analysis. Obes. Rev. 2015, 16, 341–349. [Google Scholar] [CrossRef] [Scilit]
- Ruiz-Ojeda, F.J.; Anguita-Ruiz, A.; Leis, R.; Aguilera, C.M. Genetic Factors and Molecular Mechanisms of Vitamin D and Obesity Relationship. Ann. Nutr. Metab. 2018, 73, 89–99. [Google Scholar] [CrossRef] [Scilit]
- Golzarand, M.; Hollis, B.W.; Mirmiran, P.; Wagner, C.L.; Shab-Bidar, S. Vitamin D supplementation and body fat mass: A systematic review and meta-analysis. Eur. J. Clin. Nutr. 2018, 72, 1345–1357. [Google Scholar] [CrossRef] [Scilit]
- Joukar, F.; Naghipour, M.; Hassanipour, S.; Asl, S.F.; Pourshams, A.; Mansour-Ghanaei, F. Vitamin D deficiency associated with reproductive factors in northern Iranian women: The PERSIAN Guilan Cohort Study (PGCS). Clin. Nutr. ESPEN 2020, 38, 271–276. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Andersen, L.B.; Abrahamsen, B.; Dalgård, C.; Kyhl, H.B.; Beck-Nielsen, S.S.; Frost-Nielsen, M.; Jørgensen, J.S.; Barington, T.; Christesen, H.T. Parity and tanned white skin as novel predictors of vitamin D status in early pregnancy: A population-based cohort study. Clin. Endocrinol. 2013, 79, 333–341. [Google Scholar] [CrossRef] [Scilit]
- Pilz, S.; Zittermann, A.; Obeid, R.; Hahn, A.; Pludowski, P.; Trummer, C.; Lerchbaum, E.; Pérez-López, F.R.; Karras, S.N.; März, W. The Role of Vitamin D in Fertility and during Pregnancy and Lactation: A Review of Clinical Data. Int. J. Environ. Res. Public Health 2018, 15, 2241. [Google Scholar] [CrossRef] [Scilit]
- Muscogiuri, G.; Altieri, B.; de Angelis, C.; Palomba, S.; Pivonello, R.; Colao, A.; Orio, F. Shedding new light on female fertility: The role of vitamin D. Rev. Endocr. Metab. Disord. 2017, 18, 273–283. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Manios, Y.; Moschonis, G.; Lambrinou, C.P.; Mavrogianni, C.; Tsirigoti, L.; Hoeller, U.; Roos, F.F.; Bendik, I.; Eggersdorfer, M.; Celis-Morales, C.; et al. Associations of vitamin D status with dietary intakes and physical activity levels among adults from seven European countries: The Food4Me study. Eur. J. Nutr. 2017, 57, 1357–1368. [Google Scholar] [CrossRef] [Scilit]
- Hengist, A.; Perkin, O.; Gonzalez, J.T.; Betts, J.A.; Hewison, M.; Manolopoulos, K.N.; Jones, K.S.; Koulman, A.; Thompson, D. Mobilising vitamin D from adipose tissue: The potential impact of exercise. Nutr. Bull. 2019, 44, 25–35. [Google Scholar] [CrossRef] [Scilit]
- Brock, K.; Cant, R.; Clemson, L.; Mason, R.; Fraser, D. Effects of diet and exercise on plasma vitamin D (25(OH)D) levels in Vietnamese immigrant elderly in Sydney, Australia. J. Steroid Biochem. Mol. Biol. 2007, 103, 786–792. [Google Scholar] [CrossRef] [Scilit]
- Tardelli, V.S.; Lago, M.P.P.D.; da Silveira, D.X.; Fidalgo, T.M. Vitamin D and alcohol: A review of the current literature. Psychiatry Res. 2016, 248, 83–86. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grant, W.B.; Bhattoa, H.P.; Pludowski, P. Determinants of Vitamin D Deficiency from Sun Exposure: A Global Perspective. Vitam. D Fourth Ed. 2017, 2, 79–90. [Google Scholar]
- González-Rodríguez, L.G.; Estaire, P.; Peñas-Ruiz, C.; Ortega, R.M.; UCM Research Group VALORNUT (920030). Vitamin D intake and dietary sources in a representative sample of Spanish adults. J. Hum. Nutr. Diet. 2013, 26 (Suppl. 1), 64–72. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- FESNAD. Federación Española de Sociedades de Nutrición Alimentación y Dietética. Ingestas Dietéticas de Referencia Para la Población Española; FESNAD: Madrid, Spain, 2010. [Google Scholar]
- EFSA, European Food Safety Authority. Dietary Reference Values for nutrients Summary report. EFSA Supporting Publ. 2017, 14, e15121E. Available online: https://efsa.onlinelibrary.wiley.com/doi/abs/10.2903/sp.efsa.2017.e15121 (accessed on 20 October 2021).
- Francic, V.; Ursem, S.R.; Dirks, N.F.; Keppel, M.H.; Theiler-Schwetz, V.; Trummer, C.; Pandis, M.; Borzan, V.; Grübler, M.R.; Verheyen, N.D.; et al. The Effect of Vitamin D Supplementation on its Metabolism and the Vitamin D Metabolite Ratio. Nutrients 2019, 11, 2539. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Omdahl, J.L.; Morris, H.A.; May, B.K. HYDROXYLASE ENZYMES OF THE VITAMIN D PATHWAY: Expression, Function, and Regulation. Annu. Rev. Nutr. 2002, 22, 139–166. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wagner, D.; Hanwell, H.; Schnabl, K.; Yazdanpanah, M.; Kimball, S.; Fu, L.; Sidhom, G.; Rousseau, D.; Cole, D.E.; Vieth, R. The ratio of serum 24,25-dihydroxyvitamin D3 to 25-hydroxyvitamin D3 is predictive of 25-hydroxyvitamin D3 response to vitamin D3 supplementation. J. Steroid Biochem. Mol. Biol. 2011, 126, 72–77. [Google Scholar] [CrossRef] [Scilit]
- Cashman, K.D.; Hayes, A.; Galvin, K.; Merkel, J.; Jones, G.; Kaufmann, M.; Hoofnagle, A.N.; Carter, G.D.; Durazo-Arvizu, R.A.; Sempos, C.T. Significance of serum 24, 25-dihydroxyvitamin D in the assessment of vitamin D status: A double-edged sword? Clin. Chem. 2015, 61, 636–645. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fraser, W.D.; Tang, J.; Dutton, J.J.; Schoenmakers, I. Vitamin D Measurement, the Debates Continue, New Analytes Have Emerged, Developments Have Variable Outcomes. Calcif. Tissue Int. 2019, 106, 3–13. [Google Scholar] [CrossRef] [Scilit]
- Ginsberg, C.; Katz, R.; de Boer, I.H.; Kestenbaum, B.R.; Chonchol, M.; Shlipak, M.G.; Sarnak, M.J.; Hoofnagle, A.N.; Rifkin, D.E.; Garimella, P.S.; et al. The 24,25 to 25-hydroxyvitamin D ratio and fracture risk in older adults: The cardiovascular health study. Bone 2018, 107, 124–130. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bender, R.; Lange, S. Adjusting for multiple testing—When and how? J. Clin. Epidemiol. 2001, 54, 343–349. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2021 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).