


Abstract
Objective: To synthesize and analyze the prevalence, composition, longitudinal stability, and predictors of cancer symptom clusters in children and adolescents undergoing chemotherapy. Method: A systematic literature review was conducted in accordance with the PRISMA 2020 guidelines. Evidence was sourced from MEDLINE/PubMed, Cochrane Library, Embase, PsycINFO, and Web of Science, as well as clinical trial registries (Clinical Trials WHO-ICTRP) and gray literature. The search was performed in February 2025, with no restrictions on publication date or language. Two independent reviewers screened and selected the studies. The methodological quality of the included studies was assessed using design-specific tools, and the findings were synthesized narratively. Results: A total of 6221 records were identified, with 12 studies meeting the inclusion criteria. These studies were published between 2010 and 2024 in the United States, Brazil, China, and Turkey. Cancer symptom clusters in children and adolescents followed well-defined patterns, with the gastrointestinal, emotional, fatigue-related, somatic, and self-image clusters being the most prevalent. Conclusions: Early identification of these cancer symptom clusters is essential for guiding interprofessional teams in delivering personalized, evidence-based care to children and adolescents with cancer and their families.
Keywords:
child; adolescent; neoplasms; antineoplastic agents; concurrent symptoms; oncology nursing 1. Introduction
The global age-standardized incidence, prevalence, and mortality rates of cancer in children and adolescents have declined significantly. Worldwide, 291,319 new cases and 98,834 deaths from childhood cancer have been reported, with a total of 1,806,630 prevalent cases [1]. Accurate data on the global burden of childhood and adolescent cancer are essential for informing international health policies and guiding resource allocation [2,3,4,5,6].
Pediatric cancer is often associated with symptoms that rarely occur in isolation but frequently manifest as cancer symptom clusters that are challenging to manage, including pain, nausea, vomiting, anorexia, cancer-related fatigue, depression, and anxiety, among others [7,8]. Both antineoplastic treatments and tumor progression contribute to the emergence of various symptom clusters during—and even after—treatment, adversely affecting functional status and significantly reducing quality of life [8,9,10]. The term “symptom cluster” refers to a group of interrelated symptoms that tend to occur together in a predictable pattern [11,12].
One of the key challenges in pediatric oncology nursing is the comprehensive assessment of oncological symptoms to demonstrate the significance of symptom clusters in terms of levels of interaction, association patterns, and synergistic effects [8]. The concept of a symptom cluster was first identified in murine models exposed to infectious processes and pro-inflammatory cytokines. These infectious and inflammatory responses led to the development of a phenomenon known as “sickness behavior”, a term introduced in 1992 [13,14] to describe a set of behavioral changes accompanying various pathological processes that appear to lack a direct pathophysiological link [14].
Similarly, symptoms such as fatigue, pain, sleep disturbances, depression, and cognitive impairment have been observed in children and adolescents with cancer, who exhibit elevated levels of pro-inflammatory cytokines [8,10,15].
Despite growing interest in understanding symptom clusters in oncology, existing systematic reviews have primarily focused on the adult population [16,17], or have provided only partial perspectives on pediatric oncology. While previous systematic reviews have explored aspects of symptom clusters in specific pediatric cancer contexts, they have not comprehensively synthesized evidence on the prevalence, composition, longitudinal stability, and predictors of symptom clusters in children and adolescents undergoing chemotherapy. For instance, a recent scoping review focusing on gastrointestinal symptom clusters in pediatric oncology, providing valuable insights but lacking a systematic synthesis of broader symptom clusters and their interrelationships [18]. Similarly, other researchers reviewed self-reported symptoms in children under 8 years of age, but their scope was limited to younger pediatric patients and did not analyze symptom clustering patterns in a broader age range [19]. Additionally, symptom clusters were reviewed in adolescents, but it was not a systematic review and did not examine longitudinal stability or predictive factors that influence symptom cluster trajectories [20].
Given these limitations, the present systematic review fills a critical gap by synthesizing robust evidence on cancer symptom clusters in pediatric and adolescent populations. Understanding how these clusters evolve over time and identifying predictive factors for co-occurring symptoms could provide a scientific foundation for developing personalized therapeutic interventions. Furthermore, this approach may enable the early identification of symptom patterns predictive of significant symptom clusters, ultimately contributing to improved symptom management and better quality of life during and after cancer treatment.
The aim of this study was to synthesize and analyze the prevalence, composition, longitudinal stability, and predictors of cancer symptom clusters in children and adolescents undergoing chemotherapy. By addressing these knowledge gaps, our findings have the potential to inform targeted clinical interventions and enhance supportive care strategies in pediatric oncology.
2. Method
2.1. Study Design
This study is a systematic literature review, conducted in compliance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 guidelines [21]. Additionally, the review protocol was registered with the International Prospective Register of Systematic Reviews (PROSPERO), under registration number CRD4202283141, and the protocol article was subsequently published in another journal [22].
2.2. Research Question
The research question was formulated using the PECO framework (Patient/Population, Exposure, Control or Comparison, Outcomes) [23], where P (Population) = children and adolescents (0 to 19 years) diagnosed with malignant neoplasms, E (Exposure) = chemotherapy treatment, C (Comparison) = not applicable, and O (outcomes) = prevalence, composition, longitudinal stability, and predictors of cancer symptom clusters. Based on the PECO acronym, the following guiding research question was established: “What scientific evidence is available regarding the prevalence, composition, longitudinal stability, and predictors of cancer symptom clusters in children and adolescents with cancer undergoing chemotherapy”?
2.3. Eligibility Criteria
All quantitative studies (observational and experimental studies) involving pediatric and adolescent cancer patients (0 to 19 years old) of both sexes, undergoing chemotherapy and diagnosed with any type of malignant neoplasm, were included. No restrictions on publication date or language were applied in the database search strategy. Qualitative studies and experimental studies conducted in animal models, in vivo or ex vivo, were excluded.
2.4. Search Strategy
The evidence search was conducted across the following databases: Medical Literature Analysis and Retrieval System Online (MEDLINE) via PubMed, Cochrane Library, Excerpta Medica Database (Embase), Psychology Information Database (PsycINFO), and Web of Science. Additionally, trial registry platforms such as ClinicalTrials.gov and the WHO International Clinical Trials Registry Platform were included. To enhance comprehensiveness, gray literature sources were also searched, including The British Library (UK), Google Scholar, and Preprints for Health Sciences (medRxiv). The search strategy combined controlled descriptors (database-specific indexing terms) and keywords. For MEDLINE, Medical Subject Headings (MeSH) were used; for Embase, Emtree terms were applied; and for PsycINFO, PsycINFO Thesaurus was consulted, with Boolean operators (AND/OR) used to refine the search. Table 1 provides a detailed and transparent overview of the search strategy employed in this systematic review.
Table 1.
Search strategy used in electronic databases and additional sources, on 10 February 2025. Vitória, ES, Brazil.
The Boolean operators “AND” and “OR” were used to achieve restrictive and additive combinations, respectively. Furthermore, the search was conducted using broadly expanded descriptors, without applying database filters, to ensure a comprehensive sample and minimize the risk of data loss.
2.5. Screening of Articles
Following the search, articles were exported to EndNote Web™ for storage, organization, and reference management, including duplicate identification. The retrieved studies were then exported to the Rayyan QCRI app, a screening and selection platform developed by the Qatar Computing Research Institute [24]. During the initial screening, titles and abstracts were independently reviewed by two researchers (JG and MBF) using Rayyan™. After this preliminary selection, the same two researchers independently assessed the full texts of the eligible studies to determine inclusion or exclusion. To resolve disagreements, a third reviewer, an expert in systematic review methodology (LCLJ), was consulted for arbitration in cases where the initial reviewers disagreed on study inclusion.
2.6. Data Extraction
Two reviewers, as previously mentioned, independently extracted data from the included studies using predefined data extraction forms [25,26,27]. The extracted information included the following: (a) study identification, including article title, journal impact factor, authors’ countries, year of publication, host institution (hospital, university, research center, multicenter, or single-institution study), and conflicts of interest and funding sources; (b) methodological characteristics (study objective, research question or hypotheses, study design, sample size, age, baseline characteristics of patients, recruitment method, attrition, outcome measures, follow-up duration, and statistical analyses); (c) main results and implications for clinical practice; and (d) study conclusions.
2.7. Methodological Quality Assessment
To classify the selected studies, we applied the hierarchy of evidence from the Center for Evidence-Based Medicine [28], which organizes evidence into five hierarchical levels based on study design (1A, 1B, 1C, 2A, 2B, 2C, 3A, 3B, 4, and 5). The methodological quality of studies was independently assessed by two independent reviewers, with a third reviewer resolving any disagreements. For quasi-experimental studies, the Risk of Bias in Non-randomized Studies of Interventions (ROBINS-I) tool was used [29], which evaluates bias risk across seven domains, grouped into three dimensions: pre-intervention, intervention, and post-intervention. The risk of bias is categorized as low, moderate, serious, or critical [29]. The overall ROBINS-I assessment is assigned as follows: (a) low risk of bias: comparable to a well-designed randomized trial (low bias risk across all domains); (b) moderate risk of bias: consistent with a non-randomized trial design, though not comparable to a well-designed randomized trial (low or moderate risk across all domains); (c) serious risk of bias: significant concerns in at least one domain (low or moderate risk across most domains, with at least one domain showing serious bias); (d) critical risk of bias: too problematic to provide evidence (critical risk in at least one domain); and (e) no information: insufficient data for any bias risk judgment in one or more domains [29]. For cross-sectional and longitudinal studies, we applied the JBI Critical Appraisal Checklist, following JBI recommendations [30]. The results of the included studies are presented narratively.
3. Results
3.1. Study Selection
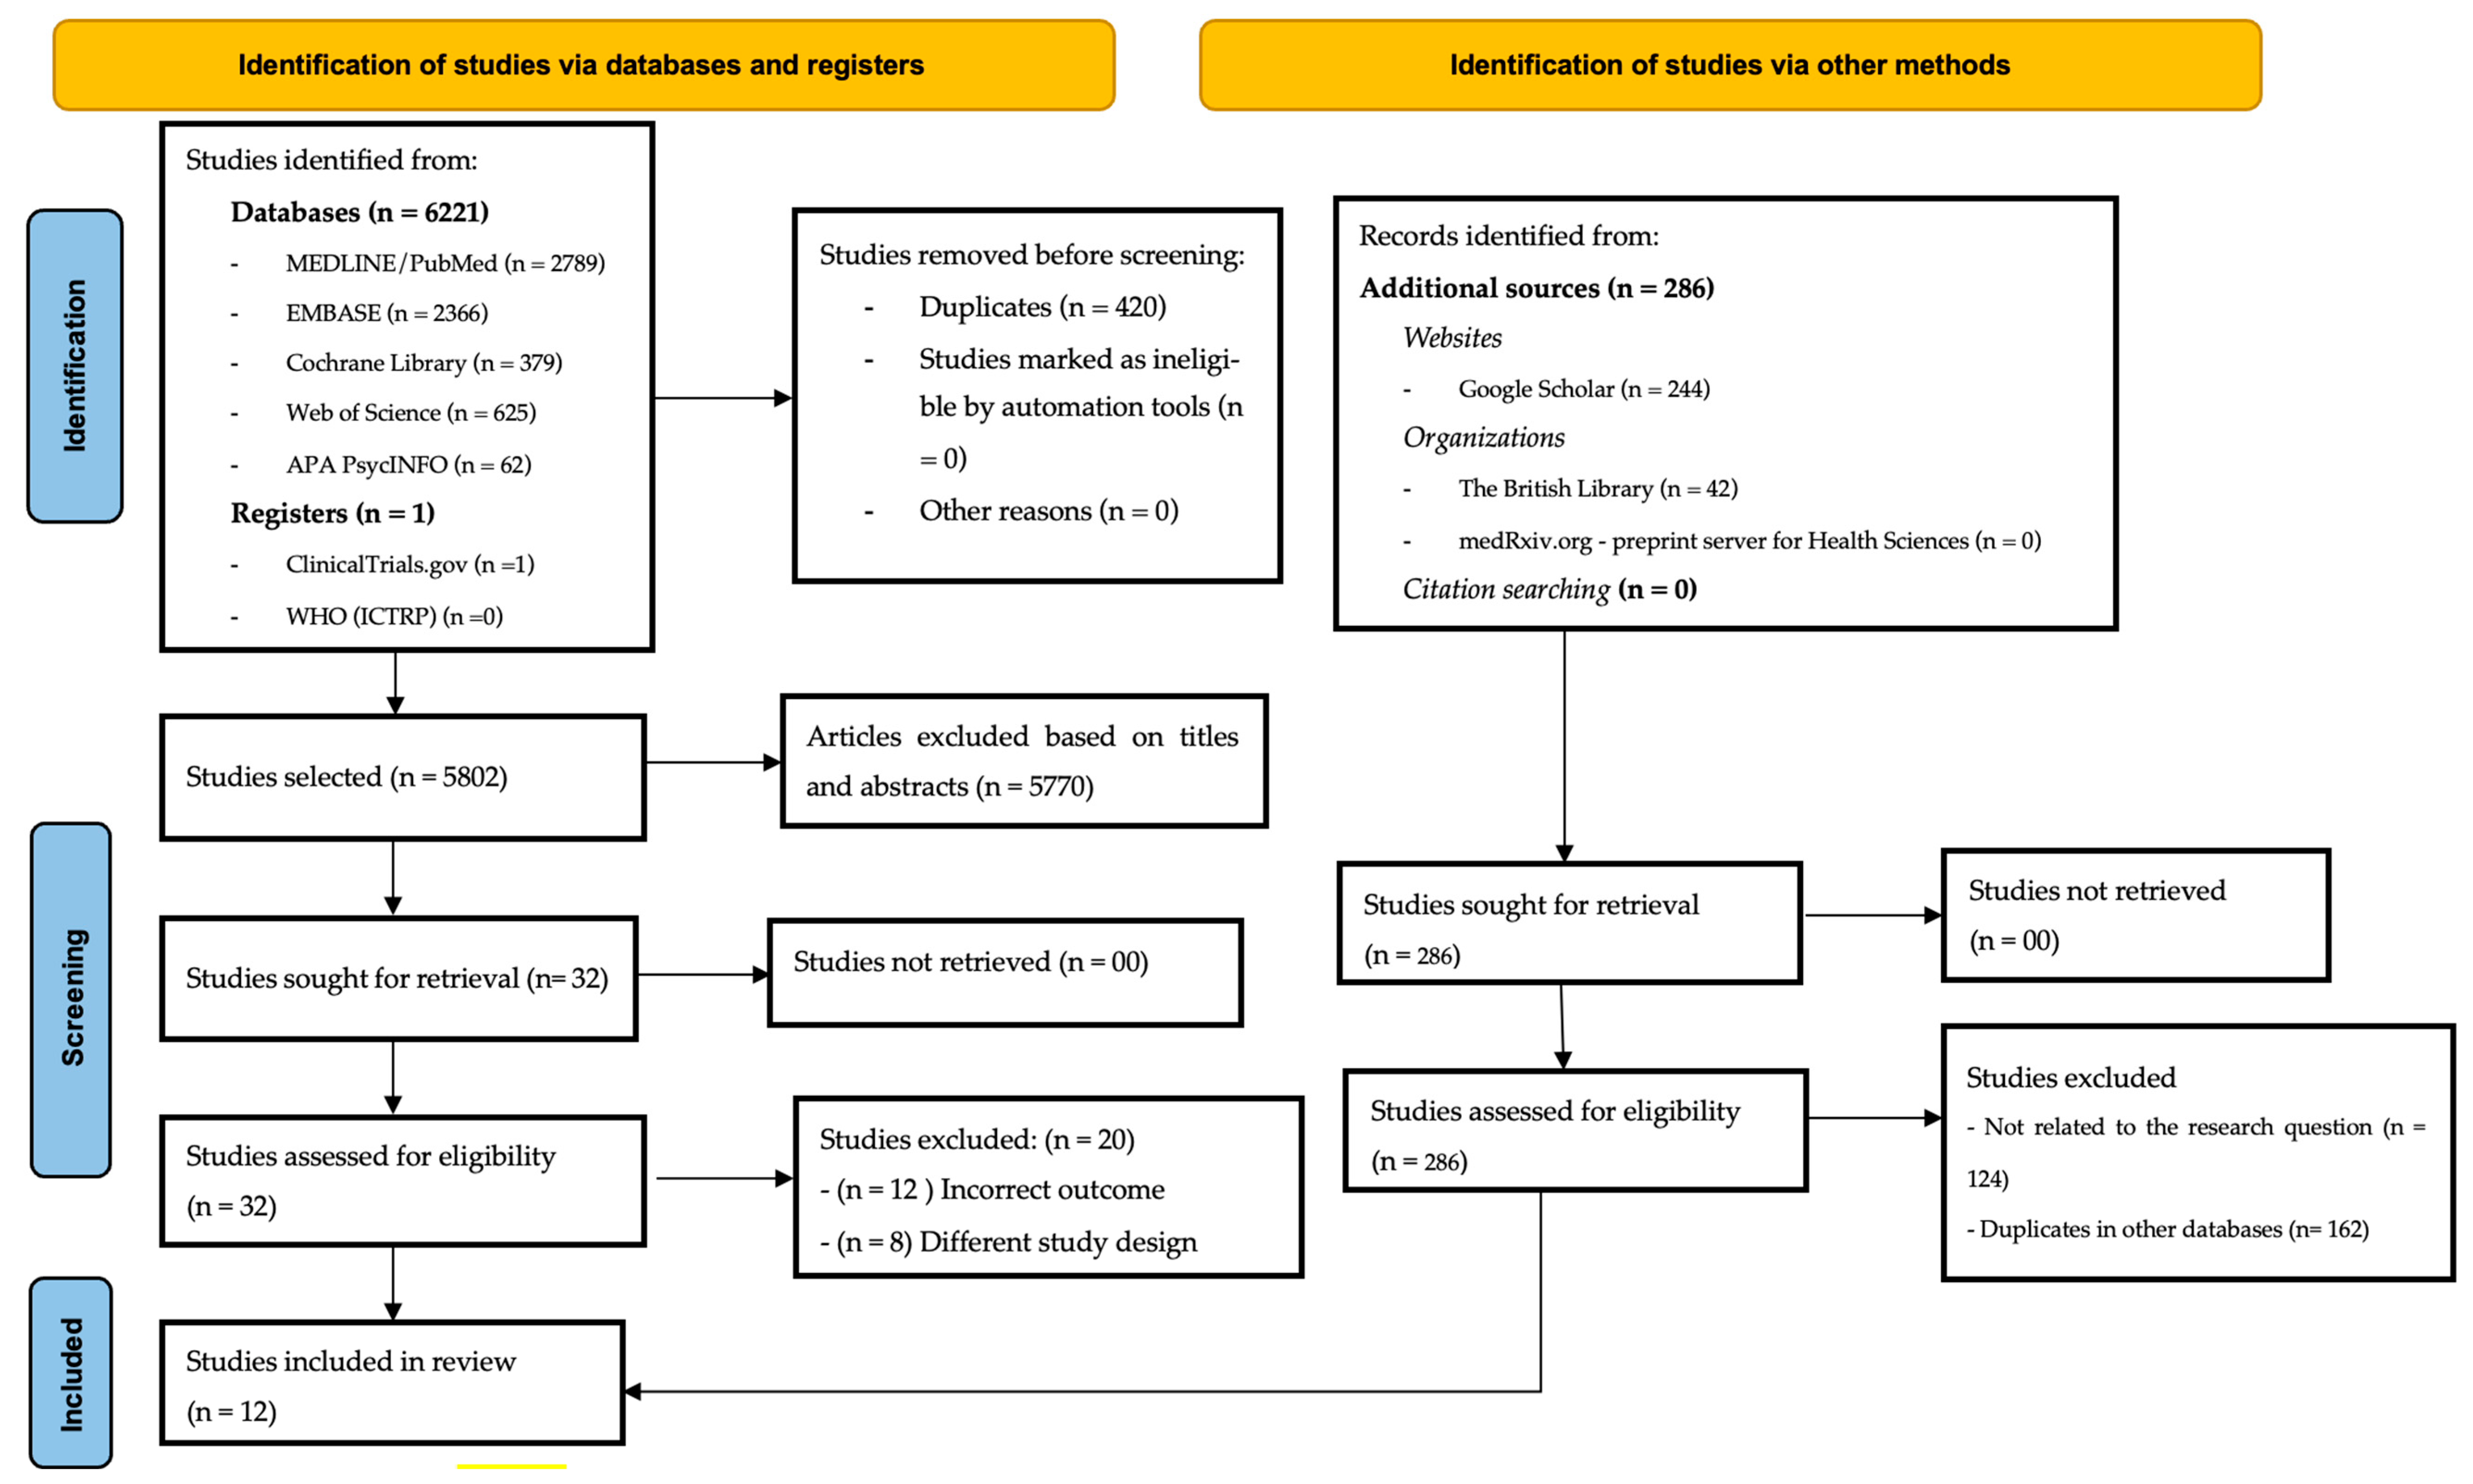
A total of 6221 records were retrieved from electronic databases and registries. After removing 420 duplicates using EndNote™, 5802 studies proceeded to the title and abstract screening phase. During this stage, conducted via Rayyan™, 5570 studies were excluded for not meeting the predefined inclusion criteria. This screening process resulted in 32 studies being selected for full-text review. Following the full-text assessment, an additional 20 studies were excluded (12 due to different outcomes and 8 based on study design), leading to the inclusion of 12 articles for qualitative synthesis and analysis, as illustrated in Figure 1.
Figure 1.
PRISMA flowchart for study selection.
3.2. Characterization of Included Studies
Among the twelve included studies [31,32,33,34,35,36,37,38,39,40,41,42], publication dates ranged from 2010 to 2024, with all studies published in English in four different countries (China, United States, Turkey, and Brazil) [31,32,33,34,35,36,37,38,39,40,41,42], six studies were cross-sectional observational designs [32,33,34,37,40,41], while four were quasi-experimental studies [31,35,36,38], and two were longitudinal studies [39,42]. Table 2 chronologically summarizes the main characteristics of the studies included in the qualitative synthesis.
Table 2.
Characteristics of the studies included in the systematic review.
This systematic review identified several symptom clusters commonly observed among children and adolescents undergoing cancer treatment. The analyzed studies indicate that these clusters vary based on cancer type, treatment phase, and individual factors, yet they exhibit consistent patterns.
- 1.
- Gastrointestinal Cluster
- The gastrointestinal cluster was one of the most frequently reported across multiple studies, encompassing symptoms such as nausea and vomiting (commonly associated with chemotherapy); diarrhea and constipation; taste alterations and dry mouth; and loss of appetite and weight loss. Studies by Li et al. [37,40,42], Wang et al. [41], and Atay et al. [33] emphasized the significance of this cluster, linking it to specific phases of chemotherapy and its adverse impact on quality of life.
- 2.
- Emotional and Psychosocial Cluster
- Another widely reported cluster involved emotional and psychological symptoms, including anxiety, worry, and nervousness; irritability and sadness; depression; and altered self-perception. This cluster was identified in several studies [31,33,35,37,39], highlighting the importance of psychological support throughout cancer treatment.
- 3.
- Fatigue and Sleep Disturbance Cluster
- Fatigue-related symptoms were highly prevalent, significantly affecting patients’ physical and emotional well-being. Key symptoms included severe and persistent fatigue; sleep disturbances and insomnia (or psychological stress); and reduced physical activity levels. This cluster was highlighted by Hockenberry et al. [31,35], Lopes-Júnior et al. [36,38], and Hooke et al. [39], with greater severity observed in adolescents diagnosed with solid tumors and those undergoing chemotherapy.
- 4.
- Somatic and Neurological Cluster
- This cluster comprised physical symptoms associated with cancer treatment, such as muscle pain and tingling sensations; headache and dizziness; and fever and excessive sweating. Studies by Li et al. [37,40,42], and Wang et al. [41] identified this cluster primarily in patients diagnosed with acute lymphoblastic leukemia (ALL).
- 5.
- Self-Image and Dermatological Cluster
- Several studies reported symptoms associated with treatment-related changes in physical appearance, including hair loss (alopecia); skin changes (dryness, itching); and swelling in the extremities. This cluster was reported by Li et al. [37,40,42], and Atay et al. [33], emphasizing the psychosocial impact of self-image alterations on pediatric oncology patients.
3.3. Internal Validity of Included Studies
Most of the quasi-experimental studies (n = 3; 75%) [33] were classified as having a low overall risk of bias, according to the ROBINS-I tool criteria. Regarding the risk of bias in the selected cross-sectional studies, which were evaluated using the JBI Critical Appraisal Checklist, all (n = 7; 87.5%) were classified as having good methodological quality. Table 3 and Table 4 provide a detailed assessment of the methodological quality of the quasi-experimental and cross-sectional studies, respectively.
Table 3.
ROBINS-I consensus assessment of quasi-experimental studies.
Table 4.
JBI checklist for analytical cross-sectional studies.
4. Discussion
The studies included in this review consolidate evidence on the prevalence, composition, longitudinal stability, and predictors of oncology symptom clusters in children and adolescents undergoing chemotherapy treatment. Across the studies, a total of 1099 participants aged 0 to 19 years were assessed. Among the symptom clusters evaluated, fatigue was the most frequently reported in all studies, followed by sleep disturbances, loss of appetite, nausea, and vomiting, respectively. In addition, five clusters were found to be more prevalent: gastrointestinal, emotional, fatigue-related, somatic, and self-image.
The instruments most commonly used for assessing oncology symptom clusters in the pediatric population were the Memorial Symptom Assessment Scale (MSAS), the Lansky Play-Performance Scale (LPPS), the Karnofsky Performance Status Scale (KPS), the Childhood Fatigue Scale (CFS), and the Pediatric Quality of Life Multidimensional Fatigue Scale (PedsQL MFS). In the methodological quality assessment, 10 studies (83.3%) demonstrated a low risk of bias, reinforcing the strong methodological rigor of the studies included in this review.
Cancer-related fatigue (CRF) is defined as a distressing and pervasive symptom with physical, mental, and emotional components, characterized by a lack of energy. It is recognized as the most common symptom experienced by children and adolescents with cancer and differs significantly from the fatigue found in the general population [39,42,43,44,45].
Among children and adolescents undergoing chemotherapy, the prevalence of cancer-related fatigue ranges from 50% to 93% [41,46,47]. Notably, CRF is not easily alleviated by sleep or rest and may persist for months or even years following the completion of cancer treatment [41,48,49]. Previous reviews have highlighted fatigue as a highly prevalent and distressing symptom that significantly impairs quality of life, becoming a barrier to daily activities, which are an essential part of childhood and adolescence [49,50,51,52,53,54,55,56]. Moreover, the use of certain medications in treatment can lead to metabolic alterations, directly affecting daily functioning. This impact is particularly pronounced in the immune system, especially through the pro-inflammatory cytokine-mediated signaling pathways [14].
A study assessing symptoms experienced by children with cancer at home identified fatigue (52.1%), nausea (50.7%), loss of appetite (43.7%), and pain (42.3%) as the most frequent physical symptoms. The most common psychological symptoms included sleep difficulties (21.1%), worry (18.3%), sadness (18.3%), and nervousness (16.9%). Significant differences were found in overall physical and psychosocial symptoms, as well as in the Global Distress Index, between patients with and without pain, fatigue, and nausea [57].
Fatigue is often regarded as an underlying driver of other distressing symptoms, given its potential to be intense, disabling, distressing, and significantly depressive [58]. Fatigue, sleep disturbance, pain, and depression are interrelated and frequently co-occur, exacerbating one another and further compromising quality of life during chemotherapy [59]. The presence of multiple concurrent physical symptoms, combined with psychological distress, leads to substantial impairment, directly interfering with daily functioning and hindering the patient’s ability to complete the prescribed cancer treatment [60].
Depression is bidirectionally associated with greater physical multimorbidity [61]. The prevalence of depression in cancer patients is 3.4 times higher than in the general population [62]. Given the high rates of anxiety and depression among children with cancer [63], emotional distress should be recognized as a sixth vital sign and routinely assessed in all cancer patients [64]. Moreover, the most significant somatic associations with depression include comorbiditiesrelated to the disease, the symptom burden related to cancer, and pain [39,65].
Sleep disturbances are common in pediatric patients [66] and frequently co-occur within the same cluster as cancer-related fatigue [39,58,67]. Sleep requirements change with age, with adolescents typically needing fewer hours of sleep than younger children [68]. These disturbances are not limited to the treatment period but can persist for more than five years following therapy [69]. Chemotherapeutic agents, steroids, and radiation therapy, which are the cornerstones of pediatric cancer treatment, play a significant role in disrupting sleep patterns[70]. A reciprocal relationship exists between sleep and pain, where pain leads to sleep disturbances and poor sleep increases pain perception [71]. Additionally, the cancer diagnosis, treatment-related consequences, and other risk factors may trigger sleep disturbances in cancer patients [66]. Hospitalization is another key factor influencing sleep quality in pediatric cancer patients. While outpatients tend to experience better sleep quality than hospitalized patients, they still face an increased risk of sleep disturbances during active treatment [71].
The quality of life of pediatric patients can be significantly affected by psychological stress [39,40,43,45,58]. As treatment progresses, critical aspects of the immune response may be suppressed, including natural killer (NK) cell activity and T cell proliferation [72]. However, psychological stress related to cancer may be alleviated through targeted interventions, such as therapeutic clowning [37].
Chemotherapy primarily targets DNA and protein expression in both cancer cells and normal host cells, resulting in a narrow therapeutic index and high risk of toxicity. Most chemotherapeutic agents affect rapidly dividing cells, particularly those in tissues with high cellular turnover, including the bone marrow, gastrointestinal tract, and hair follicles. Common toxicities associated with chemotherapy include myelosuppression, mucositis, nausea, vomiting, weight loss, diarrhea, alopecia, fatigue, among others. As a result, immunosuppression significantly increases the risk of infections [73].
The number and composition of symptom clusters in the studies included in this review varied during the first three months of treatment [34]. The most prevalent symptoms identified were dizziness, irritability, fatigue [32,34,36,37,43], nausea [32,34,36], depression [34,36], vomiting [32,34], weight loss [32,34], sleep disturbances [36], pain [36], sadness [36], anxiety-related worry [34], and psychological stress [37,43].
Although chemotherapy has led to continuous advancements in treatment, significantly improving overall survival, patients experience a broad range of physical and psychological symptoms that impact quality of life [56].
Gastrointestinal symptoms are highly prevalent among children and adolescents with cancer as well as their parents [41,74,75]. This finding is consistent with the results of this systematic review, which also identified gastrointestinal symptom cluster as one of the most prevalent in this population.
The term “gastrointestinal symptoms” encompasses symptoms directly associated with the structures and functions of the gastrointestinal tract, including dry mouth, mouth sores, difficulty swallowing, sore throat, jaw pain, nausea, vomiting, loss of appetite, changes in taste and food sensations, weight loss, diarrhea, and constipation [40,41,76,77]. Together, these symptoms contribute to feeding difficulties, which can lead to malnutrition and subsequently worsen clinical outcomes [78]. Children diagnosed with malnutrition three months after cancer diagnosis have significantly higher rates of febrile neutropenia during the first year following diagnosis and lower survival rates [79].
Loss of appetite, often induced by cancer and chemotherapy, is commonly attributed to changes in taste, mouth sores, nausea, and vomiting. These factors exacerbate other symptoms, including pain, fatigue, depression, and anxiety [80]. Functional decline associated with nutritional intake is often linked to progressive weight loss. In addition, mouth sores, pain, and poor nutrition can increase the risk of infection in immunocompromised patients [80].
A recent scoping review synthesizing findings from studies on the gastrointestinal symptom cluster and associated non-gastrointestinal symptoms in children undergoing cancer treatment revealed 12 of the most frequently reported symptoms across all clusters: nausea, changes in taste, vomiting, loss of appetite, weight loss, constipation, dry mouth, diarrhea, mouth sores, fatigue, changes in appearance, and hair loss [80].
Longitudinal stability refers to the long-term trajectory and progression of a symptom, allowing for the identification of patients’ primary needs and enabling better prevention and health promotion [81]. In children and adolescents with cancer undergoing chemotherapy with cisplatin, doxorubicin, or ifosfamide, symptoms such as cancer-related fatigue, depression, and compromised performance status can emerge as early as the first day of therapy [32]. One of the key factors influencing oncology symptom clusters during chemotherapy is the treatment stage at which patients are currently undergoing therapy [32].
The gastrointestinal and emotional symptom clusters are among the most prevalent in pediatric oncology and can persist beyond the chemotherapy phase [32,33]. Children and adolescents undergoing chemotherapy experience a wide range of persistent symptoms, with greater distress observed among those actively receiving treatment [33]. Notably, chemotherapy not only influences the formation of symptom clusters but also affects their intensity and severity. As chemotherapy cycles progress, symptom clusters in children and adolescents tend to become more intense and severe [36,38]. A comprehensive understanding of symptom clusters across different phases of cancer treatment is essential for identifying symptom stability across patient subgroups by age and over time. Such insights can inform timely clinical decisions, ultimately helping to alleviate symptom burden in children and adolescents with cancer.
It is noteworthy that several approaches have been used to identify clusters in children and adolescents with cancer, including a priori approaches (focused assessment of symptoms known to be prevalent in a particular clinical population) and de novo approaches (assessment of a wider range of symptoms to identify clusters through robust statistical analyses) [82,83]. Most studies utilizing the de novo approach applied advanced statistical techniques to identify new clusters [34,35,84]. The number of symptom clusters reported in previous studies has ranged from 1 to 10, with some inconsistencies in the composition of clusters containing similar symptoms [84,85]. Despite these inconsistencies, insights gained from symptom clusters enhance our understanding of underlying mechanisms, which could serve as potential targets for intervention [86].
The multidisciplinary team plays a crucial role in promoting the health of pediatric oncology patients [87]. Recognizing and implementing early interventions for symptom clusters is an essential component of comprehensive care.
Children and adolescents with cancer face significant challenges at individual, family, and social levels due to the disease and its treatment-related effects. This underscores the need for patient- and family-centered care [88], aimed at fostering hope and trust, providing education and support, and addressing the child’s complex needs throughout the therapeutic journey.
Parents play a crucial role in the well-being of pediatric oncology patients from the beginning of their therapeutic journey. Establishing a trusting partnership between parents and the healthcare team is essential to ensuring effective patient care. This collaboration helps parents recognize their fundamental role, encouraging their active participation in their child’s care and keeping them informed about disease progression and treatment plans [89]. Additionally, understanding the experiences of family caregivers can help healthcare professionals plan care strategies and develop interventions to mitigate symptom clusters [89,90].
A notable limitation of this review is the exclusion of certain databases, such as Scopus and CINAHL, which may have omitted relevant publications that could enhance the validity and comprehensiveness of the findings.
The experience of a cancer diagnosis is often traumatic and highly stressful for children and adolescents. The emotional, psychological, and social burdens associated with cancer coping mechanisms in this age group are significant and warrant greater attention, particularly in the context of cancer symptom clusters. Coping with cancer in childhood and adolescence presents a complex challenge that necessitates a holistic approach, integrating both clinical and psychosocial aspects of care. Providing adequate support is essential for minimizing psychosocial distress and enhancing overall well-being. Finally, the ability to predict symptom clusters in children and adolescents undergoing chemotherapy can aid in treatment decision-making, helping to alleviate symptom burden and improve quality of life in this population [38].
5. Conclusions
Findings from this systematic review indicate that cancer symptom clusters in children and adolescents follow distinct, well-defined patterns, with the gastrointestinal, emotional, fatigue, somatic, and self-image clusters being the most prevalent. Identifying these clusters is essential for developing targeted interventions to alleviate symptom burden and improve quality of life in pediatric oncology patients. The longitudinal stability of cancer symptom clusters varies depending on the disease stage and treatment phase, with inflammatory mediators, particularly pro-inflammatory and anti-inflammatory cytokines, serving as key predictors of symptom cluster configurations. Early recognition of these cancer symptom clusters is critical for guiding interdisciplinary teams in delivering personalized, patient-centered care for children and adolescents with cancer and their families.
Author Contributions
L.C.L.-J. and J.G. conceived the idea for the review. L.C.L.-J., J.G. and K.A.d.V. conducted the study selection, data extraction, methodological quality assessment, and drafted the initial manuscript. M.B.F. and F.E.S.T. contributed to the search strategy and the writing of the manuscript. J.G., M.B.F., F.E.S.T., F.A.J., K.Z.N., R.A.G.d.L., K.A.d.V. and L.C.L.-J. contributed to data interpretation, writing the manuscript, and its revisions. All authors have read and agreed to the published version of the manuscript.
Funding
This research received funding from the Espírito Santo Research and Innovation Support Foundation (FAPES), Notice FAPES No. 28/2022—UNIVERSAL, Process Number: 2023-NMV7P; the Conselho Nacional de Desenvolvimento Científico e Tecnológico (CNPq), Process Number: 406693/2023-4 (UNIVERSAL-CNPq); and the Research Productivity Fellowship of CNPq—(PQ2), Process Number: 311427/2023-5. This study was financed in part by the Coordenação de Aperfeiçoamento de Pessoal de Nível Superior—Brasil (CAPES)—Finance Code 001.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Data are available upon reasonable request.
Public Involvement Statement:
No public involvement in any aspect of this research.
Guidelines and Standards Statement:
This manuscript was drafted against the PRISMA 2020 guidelines (Page et al., 2021 [21]) for systematic reviews research.
Use of Artificial Intelligence:
AI or AI-assisted tools were not used in drafting any aspect of this manuscript.
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Wu, Y.; Deng, Y.; Wei, B.; Xiang, D.; Hu, J.; Zhao, P.; Lin, S.; Zheng, Y.; Yao, J.; Zhai, Z.; et al. Global burden of childhood cancer in 2019 and its annualized change in rates from 1990 to 2019. J. Adv. Res. 2022, 40, 233–247. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Organización Mundial de la Salud. WHO Global Initiative for Childhood with Cancer: An Overview. [Internet] Ginebra: OMS. 2020. [Cited 14 August 2023]. Available online: https://www.who.int/docs/default-source/documents/health-topics/cancer/who-childhood-cancer-overview-booklet.pdf (accessed on 15 February 2025).
- Organización Panamericana de la Salud (OPAS). La Práctica de la Enfermería Oncológica Pediátrica en América Latina y el Caribe; OPAS: Washington, DC, USA, 2022. [Google Scholar]
- Lima, R.A.G.; Lopes-Júnior, L.C.; Maia, E.B.S.; Fuentes-Alabi, S.; Ponce, M.L.V. Global Initiative for Childhood Cancer Control: Increasing access, improving quality, saving lives. Rev. Lat. Am. Enfermagem. 2023, 31, e3998. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Magrath, I.; Steliarova-Foucher, E.; Epelman, S.; Ribeiro, R.C.; Harif, M.; Li, C.K.; Kebudi, R.; Macfarlane, S.D.; Howard, S.C. Paediatric cancer in low-income and middle-income countries. Lancet Oncol. 2013, 14, e104–e116. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Day, S.; Challinor, J.; Hollis, R.; Abramovitz, L.; Hanaratri, Y.; Punjwani, R. Paediatric Oncology Nursing Care in Low-And Middle-Income Countries: A Need for Baseline Standards. [Cited 14 May 2023]. Cancer Control [Internet]. 2015, pp. 111–116. Available online: http://www.cancercontrol.info/wp-content/uploads/2015/07/111-116-Day_cc2015.pdf (accessed on 30 January 2025).
- Rodgers, C.C.; Hooke, M.C.; Taylor, O.A.; Koerner, K.M.; Mitby, P.A.; Moore, I.M.; Scheurer, M.E.; Hockenberry, M.J.; Pan, W. Childhood Cancer Symptom Cluster: Leukemia and Health-Related Quality of Life. Oncol. Nurs. Forum. 2019, 46, 228–237. [Google Scholar] [CrossRef] [Scilit]
- Kelley, K.W.; Bluthé, R.M.; Dantzer, R.; Zhou, J.H.; Shen, W.H.; Johnson, R.W.; Broussard, S.R. Cytokine-induced sickness behavior. Brain Behav. Immun. 2003, 17 (Suppl. S1), S112–S118. [Google Scholar] [CrossRef] [Scilit]
- Bhatia, S.; Landier, W. Symptom Clusters in Childhood Cancer Survivors. J. Clin. Oncol. 2023, 41, 439–442. [Google Scholar] [CrossRef] [Scilit]
- Dodd, M.J.; Miaskowski, C.; Lee, K.A. Occurrence of symptom clusters. J. Natl. Cancer Inst. Monogr. 2004, 2004, 76–78. [Google Scholar] [CrossRef] [Scilit]
- Kim, H.J.; Barsevick, A.M.; Fang, C.Y.; Miaskowski, C. Common biological pathways underlying the psychoneurological symptom cluster in cancer patients. Cancer Nurs. 2012, 35, E1–E20. [Google Scholar] [CrossRef] [Scilit]
- Kent, S.; Bluthé, R.M.; Kelley, K.W.; Dantzer, R. Sickness behavior as a new target for drug development. Trends Pharmacol. Sci. 1992, 13, 24–28. [Google Scholar] [CrossRef] [Scilit]
- Dantzer, R.; Meagher, M.W.; Cleeland, C.S. Translational approaches to treatment-induced symptoms in cancer patients. Nat. Rev. Clin. Oncol. 2012, 9, 414–426. [Google Scholar] [CrossRef] [Scilit]
- Rodgers, C.; Hooke, M.C.; Ward, J.; Linder, L.A. Symptom clusters in children and adolescents with cancer. Semin. Oncol. Nurs. 2016, 32, 394–404. [Google Scholar] [CrossRef] [Scilit]
- Dong, S.T.; Butow, P.N.; Costa, D.S.; Lovell, M.R.; Agar, M. Symptom clusters in patients with advanced cancer: A systematic review of observational studies. J. Pain. Symptom Manag. 2014, 48, 411–450. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Harris, C.S.; Kober, K.M.; Conley, Y.P.; Dhruva, A.A.; Hammer, M.J.; Miaskowski, C.A. Symptom clusters in patients receiving chemotherapy: A systematic review. BMJ Support. Palliat. Care 2022, 12, 10–21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Silva, R.J.G.; Grippa, W.R.; Pessanha, R.M.; Marcarini, J.A.C.; Silva Neto, L.C.B.; D’Agostini, N.S.; Lopes-Júnior, L.C. Cancer symptom cluster in hospitalized women with breast cancer: A descriptive observational study. Rev. Bras. Enferm. 2025, 78, e20240091. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kamkhoad, D.; Judge Santacroce, S.; Phonyiam, R.; Wang, M. Symptom Clusters That Included Gastrointestinal Symptoms Among Children Receiving Cancer Treatments: A Scoping Review. Oncol. Nurs. Forum. 2023, 50, 381–395. [Google Scholar] [CrossRef] [Scilit]
- Tomlinson, D.; Tigelaar, L.; Hyslop, S.; Lazor, T.; Dupuis, L.L.; Griener, K.; Oliveria, J.; Sung, L. Self-report of symptoms in children with cancer younger than 8 years of age: A systematic review. Support. Care Cancer 2017, 25, 2663–2670. [Google Scholar] [CrossRef] [Scilit]
- Erickson, J.M.; Macpherson, C.F.; Ameringer, S.; Baggott, C.; Linder, L.; Stegenga, K. Symptoms and symptom clusters in adolescents receiving cancer treatment: A review of the literature. Int. J. Nurs. Stud. 2013, 50, 847–869. [Google Scholar] [CrossRef] [Scilit]
- Page, M.J.; McKenzie, J.E.; Bossuyt, P.M.; Boutron, I.; Hoffmann, T.C.; Mulrow, C.D.; Shamseer, L.; Tetzlaff, J.M.; Akl, E.A.; Brennan, S.E.; et al. The PRISMA 2020 statement: An updated guideline for reporting systematic reviews. BMJ 2021, 372, n71. [Google Scholar] [CrossRef] [Scilit]
- Grassi, J.; Freitas, M.B.; Trigo, F.E.S.; Nunes, K.Z.; Lopes-Júnior, L.C. Cancer symptom clusters in pediatric patients with cancer undergoing chemotherapy: Systematic review protocol. RSD 2023, 12, e22912240188. [Google Scholar] [CrossRef] [Scilit]
- Methley, A.M.; Campbell, S.; Chew-Graham, C.; McNally, R.; Cheraghi-Sohi, S. PICO, PICOS and SPIDER: A comparison study of specificity and sensitivity in three search tools for qualitative systematic reviews. BMC Health Serv. Res. 2014, 14, 579. [Google Scholar] [CrossRef] [Scilit]
- Ouzzani, M.; Hammady, H.; Fedorowicz, Z.; Elmagarmid, A. Rayyan-a web and mobile app for systematic reviews. Syst. Rev. 2016, 5, 210. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lopes-Júnior, L.C.; Bomfim, E.; Olson, K.; Neves, E.T.; Silveira, D.S.C.; Nunes, M.D.R.; Nascimento, L.C.; Pereira-Da-Silva, G.; Lima, R.A.G. Effectiveness of hospital clowns for symptom management in paediatrics: Systematic review of randomised and non-randomised controlled trials. BMJ 2020, 371, m4290. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lopes-Júnior, L.C.; Ferrarini, T.; Pires, L.B.C.; Rodrigues, J.G.; Salaroli, L.B.; Nunes, K.Z. Cancer symptom clusters in adult patients undergoing chemotherapy: A systematic review and meta-analysis protocol. PLoS ONE 2022, 17, e0273411. [Google Scholar] [CrossRef] [Scilit]
- Higgins, J.P.T.; Thomas, J.; Chandler, J.; Cumpston, M.; Li, T.; Page, M.J.; Welch, V.A. (Eds.) Cochrane Handbook for Systematic Reviews of Interventions Version 6.5 (Updated August 2024); Cochrane: London, UK, 2024; Available online: www.training.cochrane.org/handbook (accessed on 1 April 2025).
- Centre for Evidence-Based Medicine. 2020 [Internet]. The Centre for Evidence-Based Medicine. [Cited 14 August 2023]. Available online: http://www.cebm.net (accessed on 1 April 2025).
- Sterne, J.A.C.; Hernán, M.A.; Reeves, B.C.; Savović, J.; Berkman, N.D.; Viswanathan, M.; Henry, D.; Altman, D.G.; Ansari, M.T.; Boutron, I.; et al. ROBINS-I: A tool for assessing risk of bias in non-randomised studies of interventions. BMJ 2016, 355, i4919. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Joanna Briggs Institute. Critical Appraisal Tools—JBI [Internet]. Joannabriggs.org. 2017 [Cited 14 August 2023]. Available online: https://jbi.global/critical-appraisal-tools (accessed on 13 March 2025).
- Hockenberry, M.J.; Hooke, M.C.; Gregurich, M.; McCarthy, K.; Sambuco, G.; Krull, K. Symptom clusters in children and adolescents receiving cisplatin, doxorubicin, or ifosfamide. Oncol. Nurs. Forum. 2010, 37, E16–E27. [Google Scholar] [CrossRef] [Scilit]
- Atay, S. Symptom characteristics and clustering in children and adolescents undergoing or being off cancer chemotherapy. J. BUON 2011, 16, 751–758. [Google Scholar] [PubMed]
- Atay, S.; Conk, Z.; Bahar, Z. Identifying symptom clusters in paediatric cancer patients using the Memorial Symptom Assessment Scale. Eur. J. Cancer Care 2012, 21, 460–468. [Google Scholar] [CrossRef] [Scilit]
- Baggott, C.; Cooper, B.A.; Marina, N.; Matthay, K.K.; Miaskowski, C. Symptom cluster analyses based on symptom occurrence and severity ratings among pediatric oncology patients during myelosuppressive chemotherapy. Cancer Nurs. 2012, 35, 19–28. [Google Scholar] [CrossRef] [Scilit]
- Hockenberry, M.J.; Hooke, M.C.; McCarthy, K.; Gregurich, M.A. Sickness behavior clustering in children with cancer. J. Pediatr. Oncol. Nurs. 2011, 28, 263–272. [Google Scholar] [CrossRef] [Scilit]
- Lopes-Junior, L.C.; Pereira-Da-Silva, G.; Silveira, D.S.C.; Veronez, L.C.; Santos, J.C.; Alonso, J.B.; Lima, R.A.G. The Effect of clown intervention on self-report and biomarker measures of stress and fatigue in pediatric osteosarcoma inpatients: A pilot study. Integr. Cancer Ther. 2018, 17, 928–940. [Google Scholar] [CrossRef] [Scilit]
- Li, R.; Ma, J.; Chan, Y.; Yang, Q.; Zhang, C. Symptom Clusters and Influencing Factors in Children With Acute Leukemia During Chemotherapy. Cancer Nurs. 2020, 43, 411–418. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lopes-Junior, L.C.; Silveira, D.S.C.; Olson, K.; Bomfim, E.O.; Veronez, L.C.; Santos, J.C.; Alonso, J.B.; Nascimento, L.C.; Pereira-Da-Silva, G.; Lima, R.A.G. Clown intervention on psychological stress and fatigue in pediatric patients with cancer undergoing chemotherapy. Cancer Nurs. 2020, 43, 290–299. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hooke, M.C.P.; Mathiason, M.A.; Blommer, A.B.; Hutter, J.B.; Mitby, P.; Taylor, O.; Scheurer, M.E.; Kunin-Batson, A.S.; Pan, W.; Hockenberry, M.J.P. Symptom clusters, physical activity, and quality of life. Cancer Nurs. 2022, 45, 113–119. [Google Scholar] [CrossRef] [Scilit]
- Li, R.M.; Yao, W.M.; Chan, Y.M.; Shen, M.M.; Wang, X.M.; Wen, F.M.; Yang, Q.M. Correlation between symptom clusters and quality of life in children with acute leukemia during chemotherapy. Cancer Nurs. 2022, 45, 96–104. [Google Scholar] [CrossRef] [Scilit]
- Wang, Y.; Xie, H.; Jiang, H.; Chen, M.; Ren, L.; Dong, C. Analyzing the symptom clusters among children with acute lymphoblastic leukemia during chemotherapy based on electronic nursing records. Cancer Nurs. 2025, 48, 138–146. [Google Scholar] [CrossRef] [Scilit]
- Li, R.; Shen, X.M.; Yang, Q.M.; Zhang, L.M.; Li, H.; Yao, W.M.; Chan, Y.M. Stability of symptom clusters in children with acute lymphoblastic leukemia undergoing chemotherapy. Cancer Nurs. 2024, 47, 48–59. [Google Scholar] [CrossRef] [Scilit]
- Hockenberry-Eaton, M.; Hinds, P.S. Fatigue in children and adolescents with cancer: Evolution of a program of study. Semin. Oncol. Nurs. 2000, 16, 261–272; discussion 272–278. [Google Scholar] [CrossRef] [Scilit]
- Thong, M.S.Y.; van Noorden, C.J.F.; Steindorf, K.; Arndt, V. Cancer-Related Fatigue: Causes and Current Treatment Options. Curr. Treat. Options Oncol. 2020, 21, 17. [Google Scholar] [CrossRef] [Scilit]
- Al Maqbali, M. Cancer-related fatigue: An overview. Br. J. Nurs. 2021, 30, S36–S43. [Google Scholar] [CrossRef] [Scilit]
- Levesque, A.; Caru, M.; Duval, M.; Laverdière, C.; Sultan, S. Contributors to cancer-related fatigue in childhood cancer survivors and the use of non-pharmacological interventions: A scoping review protocol. JBI Evid. Synth. 2021, 19, 2423–2433. [Google Scholar] [CrossRef] [Scilit]
- Kelada, L.; Wakefield, C.; Heathcote, L.; Jaaniste, T.; Signorelli, C.; Fardell, J.; Donoghoe, M.; McCarthy, M.; Gabriel, M.; Cohn, R. Perceived cancer-related pain and fatigue, information needs, and fear of cancer recurrence among adult survivors of childhood cancer. Patient Educ. Couns. 2019, 102, 2270–2278. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fabi, A.; Bhargava, R.; Fatigoni, S.; Guglielmo, M.; Horneber, M.; Roila, F.; Weis, J.; Jordan, K.; Ripamonti, C.I.; ESMO Guidelines Committee. Cancer-related fatigue: ESMO Clinical Practice Guidelines for diagnosis and treatment. Ann. Oncol. 2020, 31, 713–723. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ma, Y.; He, B.; Jiang, M.; Yang, Y.; Wang, C.; Huang, C.; Han, L. Prevalence and risk factors of cancer-related fatigue: A systematic review and meta-analysis. Int. J. Nurs. Stud. 2020, 111, 103707. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kang, Y.E.; Yoon, J.H.; Park, N.H.; Ahn, Y.C.; Lee, E.J.; Son, C.G. Prevalence of cancer-related fatigue based on severity: A systematic review and meta-analysis. Sci. Rep. 2023, 13, 12815. [Google Scholar] [CrossRef] [Scilit]
- Kestler, S.A.; LoBiondo-Wood, G. Review of symptom experiences in children and adolescents with cancer. Cancer Nurs. 2012, 35, E31–E49. [Google Scholar] [CrossRef] [Scilit]
- Nowe, E.; Stöbel-Richter, Y.; Sender, A.; Leuteritz, K.; Friedrich, M.; Geue, K. Cancer-related fatigue in adolescents and young adults: A systematic review of the literature. Crit. Rev. Oncol. Hematol. 2017, 118, 63–69. [Google Scholar] [CrossRef] [Scilit]
- Spathis, A.; Booth, S.; Grove, S.; Hatcher, H.; Kuhn, I.; Barclay, S. Teenage and Young Adult Cancer-Related Fatigue Is Prevalent, Distressing, and Neglected: It Is Time to Intervene. A Systematic Literature Review and Narrative Synthesis. J. Adolesc. Young Adult Oncol. 2015, 4, 3–17. [Google Scholar] [CrossRef] [Scilit]
- Tomlinson, D.; Zupanec, S.; Jones, H.; O’Sullivan, C.; Hesser, T.; Sung, L. The lived experience of fatigue in children and adolescents with cancer: A systematic review. Support. Care Cancer 2016, 24, 3623–3631. [Google Scholar] [CrossRef] [Scilit]
- Hooke, M.C.; Linder, L.A. Symptoms in Children Receiving Treatment for Cancer-Part I: Fatigue, Sleep Disturbance, and Nausea/Vomiting. J. Pediatr. Oncol. Nurs. 2019, 36, 244–261. [Google Scholar] [CrossRef] [Scilit]
- Antill Keener, T. Childhood Cancer-Related Fatigue and Day-to-Day Quality of Life. J. Pediatr. Oncol. Nurs. 2019, 36, 74–85. [Google Scholar] [CrossRef] [Scilit]
- Dsilva, F.; Singh, P.; Javeth, A. Determinants of Cancer-Related Fatigue among Cancer Patients: A Systematic Review. J. Palliat. Care 2023, 38, 432–455. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, A.B.; Housley, S.N.; Flores, A.M.; Kircher, S.M.; Perreault, E.J.; Cope, T.C. A review of movement disorders in chemotherapy-induced neurotoxicity. J. Neuroeng. Rehabil. 2021, 18, 16. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vichaya, E.G.; Chiu, G.S.; Ekrukowski, K.; Lacourt, T.E.; Ekavelaars, A.; Dantzer, R.; Heijnen, C.J.; Walker, A.K. Mechanisms of chemotherapy-induced behavioral toxicities. Front. Neurosci. 2015, 9, 131. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stubbs, B.; Vancampfort, D.; Veronese, N.; Kahl, K.G.; Mitchell, A.J.; Lin, P.-Y.; Tseng, P.-T.; Mugisha, J.; Solmi, M.; Carvalho, A.F.; et al. Depression and physical health multimorbidity: Primary data and country-wide meta-analysis of population data from 190 593 people across 43 low- and middle-income countries. Psychol. Med. 2017, 47, 2107–2117. [Google Scholar] [CrossRef] [Scilit]
- Hartung, T.; Brähler, E.; Faller, H.; Härter, M.; Hinz, A.; Johansen, C.; Keller, M.; Koch, U.; Schulz, H.; Weis, J.; et al. The risk of being depressed is significantly higher in cancer patients than in the general population: Prevalence and severity of depressive symptoms across major cancer types. Eur. J. Cancer 2017, 72, 46–53. [Google Scholar] [CrossRef] [Scilit]
- Yardeni, M.; Campino, G.A.; Hasson-Ohayon, I.; Basel, D.; Hertz-Palmor, N.; Bursztyn, S.; Weisman, H.; Pessach, I.M.; Toren, A.; Gothelf, D. Trajectories and risk factors for anxiety and depression in children and adolescents with cancer: A 1-year follow-up. Cancer Med. 2021, 10, 5653–5660. [Google Scholar] [CrossRef] [Scilit]
- Lazor, T.; Pole, J.D.; De Souza, C.; Schechter, T.; Grant, R.; Davis, H.; Duong, N.; Stein, E.; Cook, S.; Tigelaar, L.; et al. Severity, change over time, and risk factors of anxiety in children with cancer depend on anxiety instrument used. Psychooncology 2019, 28, 710–717. [Google Scholar] [CrossRef] [Scilit]
- Riedl, D.; Schüßler, G. Factors associated with and risk factors for depression in cancer patients—A systematic literature review. Transl. Oncol. 2022, 16, 101328. [Google Scholar] [CrossRef] [Scilit]
- Daniel, L.C.; Aggarwal, R.; Schwartz, L.A. Sleep in Adolescents and Young Adults in the Year After Cancer Treatment. J. Adolesc. Young Adult Oncol. 2017, 6, 560–567. [Google Scholar] [CrossRef] [Scilit]
- Tucker, P.; Loew, M.; Russell, K.; Tynes, B.L.; Mandrell, B.N.; Witcraft, S.M.; Schwartz, L.E.; Crabtree, V.M. Sleep health behaviors in pediatric patients with newly diagnosed cancer. J. Psychosom. Res. 2023, 172, 111413. [Google Scholar] [CrossRef] [Scilit]
- Sheikh, I.N.; Roth, M.; Stavinoha, P.L. Prevalence of Sleep Disturbances in Pediatric Cancer Patients and Their Diagnosis and Management. Children 2021, 8, 1100. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Clanton, N.R.; Klosky, J.L.; Li, C.; Jain, N.; Srivastava, D.K.; Mulrooney, D.; Zeltzer, L.; Stovall, M.; Robison, L.L.; Krull, K.R. Fatigue, vitality, sleep, and neurocognitive functioning in adult survivors of childhood cancer: A report from the Childhood Cancer Survivor Study. Cancer 2011, 117, 2559–2568. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Xavier, W.D.S.; Abreu, M.P.; Nunes, M.D.R.; Silva-Rodrigues, F.M.; da Silva, L.F.; de Araújo, B.B.M.; De Bortoli, P.S.; Neris, R.R.; Nascimento, L.C. The Sleep Patterns of Children and Adolescents with Chronic Conditions and Their Families: An Integrative Literature Review. Children 2024, 11, 207. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lee, S.; Narendran, G.; Tomfohr-Madsen, L.; Schulte, F. A systematic review of sleep in hospitalized pediatric cancer patients. Psychooncology 2017, 26, 1059–1069. [Google Scholar] [CrossRef] [Scilit]
- Chandwani, K.D.; Ryan, J.L.; Peppone, L.J.; Janelsins, M.M.; Sprod, L.K.; Devine, K.; Trevino, L.; Gewandter, J.; Morrow, G.R.; Mustian, K.M. Cancer-related stress and complementary and alternative medicine: A review. Evid. Based Complement. Altern. Med. 2012, 2012, 979213. [Google Scholar] [CrossRef] [Scilit]
- Amjad, M.T.; Chidharla, A.; Kasi, A. Cancer Chemotherapy. 3 March 2022. In StatPearls [Internet]; StatPearls Publishing: Treasure Island, FL, USA, 2022; [Cited 14 August 2023]. Available online: https://pubmed.ncbi.nlm.nih.gov/33232037/ (accessed on 1 April 2025).
- Johnston, D.L.; Hyslop, S.; Tomlinson, D.; Baggott, C.; Gibson, P.; Orsey, A.; Dix, D.; Price, V.; Vanan, M.; Portwine, C.; et al. Describing symptoms using the Symptom Screening in Pediatrics Tool in hospitalized children with cancer and hematopoietic stem cell transplant recipients. Cancer Med. 2018, 7, 1750–1755. [Google Scholar] [CrossRef] [Scilit]
- Linder, L.A.; Al-Qaaydeh, S.; Donaldson, G. Symptom Characteristics Among Hospitalized Children and Adolescents With Cancer. Cancer Nurs. 2018, 41, 23–32. [Google Scholar] [CrossRef] [Scilit]
- Collins, J.J.; Byrnes, M.E.; Dunkel, I.J.; Lapin, J.; Nadel, T.; Thaler, H.T.; Polyak, T.; Rapkin, B.; Portenoy, R.K. The measurement of symptoms in children with cancer. J. Pain. Symptom Manag. 2000, 19, 363–377. [Google Scholar] [CrossRef] [Scilit]
- Williams, P.D.P.; Williams, A.R.P.; Kelly, K.P.P.; Dobos, C.P.; Gieseking, A.B.; Connor, R.M.; Ridder, L.M.; Potter, N.M.; Del Favero, D.M. A symptom checklist for children with cancer: The Therapy-Related Symptom Checklist-Children. Cancer Nurs. 2012, 35, 89–98. [Google Scholar] [CrossRef] [Scilit]
- Green, R.; Horn, H.; Erickson, J.M. Eating experiences of children and adolescents with chemotherapy-related nausea and mucositis. J. Pediatr. Oncol. Nurs. 2010, 27, 209–216. [Google Scholar] [CrossRef] [Scilit]
- Loeffen, E.A.; Brinksma, A.; Miedema, K.G.; de Bock, G.H.; Tissing, W.J. Clinical implications of malnutrition in childhood cancer patients--infections and mortality. Support. Care Cancer 2015, 23, 143–150. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chui, P.L. Cancer- and Chemotherapy-Related Symptoms and the Use of Complementary and Alternative Medicine. Asia Pac. J. Oncol. Nurs. 2019, 6, 4–6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hariyanto, T.I.; Kurniawan, A. Appetite problem in cancer patients: Pathophysiology, diagnosis, and treatment. Cancer Treat. Res. Commun. 2021, 27, 100336. [Google Scholar] [CrossRef] [Scilit]
- Baratieri, T.; Marcon, S.S. Longitudinality of care: Perceptions of the nurses that work at the family health strategy. Esc. Anna Nery. 2011, 15, 802–810. [Google Scholar] [CrossRef] [Scilit]
- Miaskowski, C. Future Directions in Symptom Cluster Research. Semin. Oncol. Nurs. 2016, 32, 405–415. [Google Scholar] [CrossRef] [Scilit]
- Yeh, C.H.; Chiang, Y.C.; Chien, L.C.; Lin, L.; Yang, C.P.; Chuang, H.L. Symptom clustering in older Taiwanese children with cancer. Oncol. Nurs. Forum. 2008, 35, 273–281. [Google Scholar] [CrossRef] [Scilit]
- Lopes-Júnior, L.C. Cancer symptom clusters: From the lab bench to clinical practice. Rev. Bras. Enferm. 2022, 75, e2022v75n5inov. [Google Scholar] [CrossRef] [Scilit]
- Kwekkeboom, K.L. Cancer Symptom Cluster Management. Semin. Oncol. Nurs. 2016, 32, 373–382. [Google Scholar] [CrossRef] [Scilit]
- Tanaka, H.; Medeiros, G.; Giglio, A. Multidisciplinary teams: Perceptions of professionals and oncological patients. Rev. Assoc. Med. Bras. 2020, 66, 419–423. [Google Scholar] [CrossRef] [Scilit]
- Al-Motlaq, M.A.; Carter, B.; Neill, S.; Hallstrom, I.K.; Foster, M.; Coyne, I.; Arabiat, D.; Darbyshire, P.; Feeg, V.D.; Shields, L. Toward developing consensus on family-centred care: An international descriptive study and discussion. J. Child. Health Care 2019, 23, 458–467. [Google Scholar] [CrossRef] [Scilit]
- Enskär, K.; Darcy, L.; Björk, M.; Knutsson, S.; Huus, K. Experiences of Young Children with Cancer and Their Parents with Nurses’ Caring Practices During the Cancer Trajectory. J. Pediatr. Oncol. Nurs. 2020, 37, 21–34. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cheng, L.; Wang, L.; He, M.; Feng, S.; Zhu, Y.; Rodgers, C. Perspectives of children, family caregivers, and health professionals about pediatric oncology symptoms: A systematic review. Support. Care Cancer 2018, 26, 2957–2971. [Google Scholar] [CrossRef] [Scilit]
- Vitorino, L.M.; Lopes-Júnior, L.C.; de Oliveira, G.H.; Tenaglia, M.; Brunheroto, A.; Cortez, P.J.O.; Lucchetti, G. Spiritual and religious coping and depression among family caregivers of pediatric cancer patients in Latin America. Psychooncology 2018, 27, 1900–1907. [Google Scholar] [CrossRef] [Scilit] [PubMed]

Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2025 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).