


Abstract
Background: To investigate associations between psychological problems and the use of healthcare and informal care and total costs among head and neck cancer (HNC) patients. Method: Data were used of the NETherlands QUality of Life and Biomedical Cohort study. Anxiety and depression disorder (diagnostic interview), distress, symptoms of anxiety and depression (HADS), and fear of cancer recurrence (FCR) and cancer worry scale (CWS) were measured at baseline and at 12-month follow-up. Care use and costs (questionnaire) were measured at baseline, 3-, 6-, 12-, and 24-month follow-up. Associations between psychological problems and care use/costs were investigated using logistic and multiple regression analyses. Results: Data of 558 patients were used. Distress, symptoms of anxiety or depression, FCR, and/or anxiety disorder at baseline were significantly associated with higher use of primary care, supportive care, and/or informal care (odds ratios (ORs) between 1.55 and 4.76). Symptoms of anxiety, FCR, and/or depression disorder at 12-month follow-up were significantly associated with use of primary care, supportive care, and/or informal care (ORs between 1.74 and 6.42). Distress, symptoms of anxiety, and FCR at baseline were associated with higher total costs. Discussion: HNC patients with psychological problems make more use of healthcare and informal care and have higher costs. This is not the result of worse clinical outcomes.
1. Introduction
Head and neck cancer (HNC) patients are prone to psychological problems. In this exploratory study, psychological problems are defined as symptoms of depression, symptoms of anxiety, distress, fear of cancer recurrence (FCR), depression disorder, or anxiety disorder. Prevalence rates of distress range from 29% to 53% [1,2,3]. It is estimated that symptoms of anxiety are present in approximately 10% to 29% [4,5], and symptoms of depression in 15% to 50%, of HNC patients [5,6,7,8,9,10]. Prevalence rate of high FCR is estimated at 53% among HNC patients [11]. These psychological problems, besides influencing a patients’ health-related quality of life [12], may also have economic consequences due to higher healthcare use [13].
Carlson and Bultz [13] previously suggested that cancer patients with psychological problems not only have increased mental healthcare use, but may also make more use of other healthcare domains, such as inpatient healthcare and general practitioner visits. A recent systematic review investigating psychological problems in relation to healthcare and societal costs among cancer patients in general, supported this suggestion [14]. This review showed that there is strong evidence for a significant association between anxiety and depression disorders and increased inpatient and outpatient healthcare use. When focusing on psychological symptoms (rather than disorders), FCR was found to be significantly associated with increased primary care use [15]. For other associations between psychological symptoms (FCR, distress, symptoms of depression, and symptoms of anxiety) and healthcare use (inpatient, primary, mental, and supportive care) the results were inconclusive due to inconsistent findings or limited evidence available [14]. No studies were conducted that investigated the association between psychological problems and informal care use. This review also showed that most previous research was conducted among breast cancer patients and cancer patients in general, and only a few studies targeted other specific tumor sites, such as HNC. Existing evidence on the associations between psychological problems and healthcare use may not be representative of HNC patients, as differences in sociodemographic and clinical characteristics, and differences in the prevalence of psychological problems, may influence this association. Furthermore, as studies have shown that HNC patients report one of the highest prevalences of any mental disorder in a life time and currently among all cancer types [10,16], investigating the relationship between healthcare use and costs among this cancer patient subgroup is especially important. So far, only two studies have investigated the association between psychological problems and medical healthcare use among HNC patients [17,18]. A cross-sectional study by Laurence et al. [18] found that, among 34,153 HNC patients, depression disorder was associated with more hospital admissions. Another cross-sectional study by Jeffery et al. found that, among 2944 HNC patients, depression and anxiety disorders were associated with more hospital admissions, ambulatory visits, and the number of bed days in hospital [17]. However, there are no longitudinal studies to date that investigate the association between psychological problems and mental healthcare, primary care, supportive care, and/or informal care among HNC patients.
This exploratory study aimed to investigate the relationship between psychological problems in relation to healthcare utilization (mental healthcare, primary care, and supportive care), use of informal care, and the costs, from baseline (before the start of treatment) up to 2 years after treatment, among HNC patients.
2. Materials & Methods
2.1. Patients and Procedure
Data from the NETherlands QUality of Life and Biomedical Cohort (NET-QUBIC), an ongoing prospective observational cohort study among newly diagnosed HNC patients in the Netherlands, were used [19]. Patients were recruited between March 2014 and June 2018. Patients were included in NET-QUBIC if they were (1) 18 years or older; (2) treated with curative intent for cancer of the oral cavity, oropharynx, hypopharynx, larynx, or unknown primary; (3) able to write, read, and speak Dutch; and (4) if they completed the medical consumption questionnaire (iMCQ) at baseline. Exclusion criteria were severe psychiatric comorbidities (schizophrenia, Korsakoff’s syndrome, severe dementia). Consent procedures were approved by the Medical Ethical Committee of VUmc and followed the Dutch Medical Research Involving Human Subjects Act (METc VUmc 2013.301). The NET-QUBIC Data Warehouse comprises data derived from an electronic clinical report form (eCRF) (assessed at baseline, 24-, and 60-month follow-up); patient-reported outcome measures (PROMs); at baseline (shortly after diagnosis and before start of treatment); at 3-, 6-, 12-, 24-, 36-, 48-, and 60-month follow-up (after finishing cancer treatment); and fieldwork assessments (at baseline, 6-, 12-, 24-, and 60-month follow-up). In this study, baseline eCRF data were used, as well as PROM data collected at baseline and at 3-, 6-, 12-, and 24-month follow-up. From the fieldwork assessments, we used data from the psychiatric interview (Composite International Diagnostic Interview (CIDI)) collected at baseline and at 12-month follow-up.
2.2. Outcome Measures
Demographic and clinical characteristics were collected by PROMs and eCRF data. Demographic factors included sex, age, education (low/middle/high), and living status (alone/cohabiting). Clinical factors included tumor location (oral cavity/oropharynx, hypopharynx, larynx), tumor stage (0–II/III–IV), treatment modality (single/multimodality treatment), World Health Organization performance status (0, able to carry out all normal activity without restriction; ≥1, restricted in normal activities). Comorbidity was assessed by the 27-item Adult Comorbidity Evaluation-27 Index, which categorizes comorbidity as none–mild, and moderate–severe [20].
Symptoms of anxiety, depression, and distress were measured with the Hospital Anxiety and Depression Scale (HADS). The HADS is a 14-item questionnaire measuring symptoms of anxiety (subscale HADS-A) and depression (subscale HADS-D) [21]. Patients respond to all items on a 4-point Likert scale, resulting in a subscale score ranging from 0 to 21. A higher score indicates higher extent of depression or anxiety symptoms. A subscale score of ≥8 was used to identify patients with symptoms of anxiety or depression. A total score of ≥11 was used to identify patients with distress. Internal consistency in this study was good (Cronbach’s alpha ranged from 0.78 to 0.89).
Fear of cancer recurrence was measured with the Cancer Worry Scale (CWS) (22). The CWS is an 8-item questionnaire measuring concerns about developing cancer or developing cancer again, and the effect of these concerns on daily life. Patients respond to all items on a 4-point Likert scale, resulting in a subscale score ranging from 8 to 32. A higher score indicates higher extent of FCR. A cut-off at ≥14 for the total score was used to identify patients with a high level of FCR [22]. The Dutch version of CWS is validated in various cancer populations [23,24]. Internal consistency was good in this HNC study population (Cronbach’s alpha was 0.89). Anxiety disorder and depression disorder in the past 6 (baseline) or 12 (12-month follow-up) months was assessed with the Composite International Diagnostic Interview (CIDI), which is based on DSM-IV criteria [25]. Fieldworkers from different backgrounds (e.g., nurse, dietician, psychologist) were trained to conduct the CIDI in a standardized way. All CIDI interviews were audiotaped and randomly checked for their quality. Healthcare use was measured with the iMCQ developed by the Institute for Medical Technology Assessment (iMTA) of the Erasmus University Rotterdam, the Netherlands [26,27]. This questionnaire measures healthcare use with a recall period of 3 months. In this study, we specifically investigated the use of (1) mental healthcare (psychiatrist, psychologist, or psychotherapist visits); (2) primary care (general practitioner visits and phone calls; (3) supportive care (physiotherapy, speech therapy, oral hygiene care, dietetics, social work, support groups); and (4) informal care (support from family, friends, neighbors, colleagues). In cases where data on the number of visits were missing (e.g., a patient reported to have visited a general practitioner, but did not report the number of visits), assumptions were made based on the means of participants who used this type of care, per measurement.
Total costs (mental healthcare, primary care, supportive care, and informal care costs) were calculated by multiplying resource use by the integral cost price from a Dutch cost price manual [28]. All prices were converted to 2018 prices using the consumer price index.
2.3. Statistical Analysis
Baseline characteristics of the study population are described using their mean and standard deviation, and percentage. Differences between included and excluded patients were investigated using independent t-tests for continuous variables and chi-square tests for categorical variables. A p-value lower than 0.05 was considered statistically significant. Associations between psychological problems and healthcare use (yes/no) were analyzed using chi-square tests (univariate analyses) and logistic regression analyses (multivariate analyses). Scores on symptoms of anxiety and depression, distress, and fear of recurrence were dichotomized based on validated cut-off scores, as described above. The potential confounding role of age, sex, living status, education level, tumor site, tumor stage, treatment, performance status, and comorbidity were investigated using forward logistic regression analyses. Only potential confounding factors that were significantly associated with healthcare use (p-value for entry of <0.05) were included in the final multivariate model. Odds ratios (OR) were calculated as a measure of effect size, and represent the increased odds for care use in HNC patients with psychological problems compared to those without.
The association between psychological problems and healthcare costs was analyzed using multiple regression analyses corrected for all above-mentioned variables. Since cost data are usually characterized by a non-normal distribution and high variance, studies are seldom powered to detect significant differences in costs among groups [29]. Therefore, a probabilistic approach was used. Bias-corrected and accelerated bootstrap confidence intervals (BCa CI) were generated by replicating the regression analyses using bias-corrected and accelerated bootstrapping with 5000 replications.
Analyses were carried out investigating psychological problems before treatment in relation to care use and costs at baseline, as well as at 3-, 6-, 12-, and 24-month follow-up. Furthermore, analyses were carried out investigating psychological problems at 12 months after treatment in relation to care use and costs at 12- and 24-month follow-up. All statistical analyses were conducted using the IBM Statistical Package for the Social Sciences (SPSS) version 26 (IBM Corp., Armonk, NY, USA) and R version 4.0.3 (The R Foundation for Statistical Computing, Vienna, Austria).
3. Results
3.1. Study Population
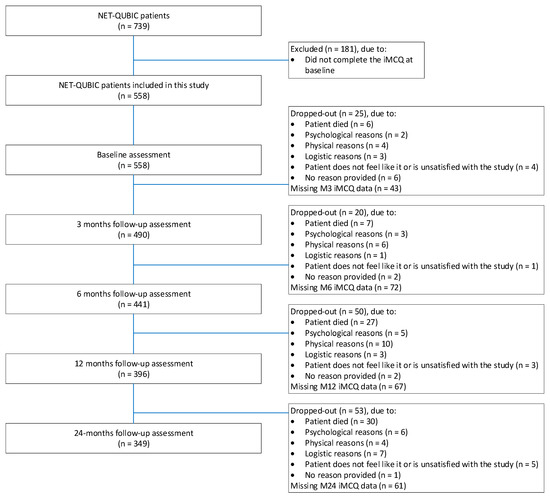
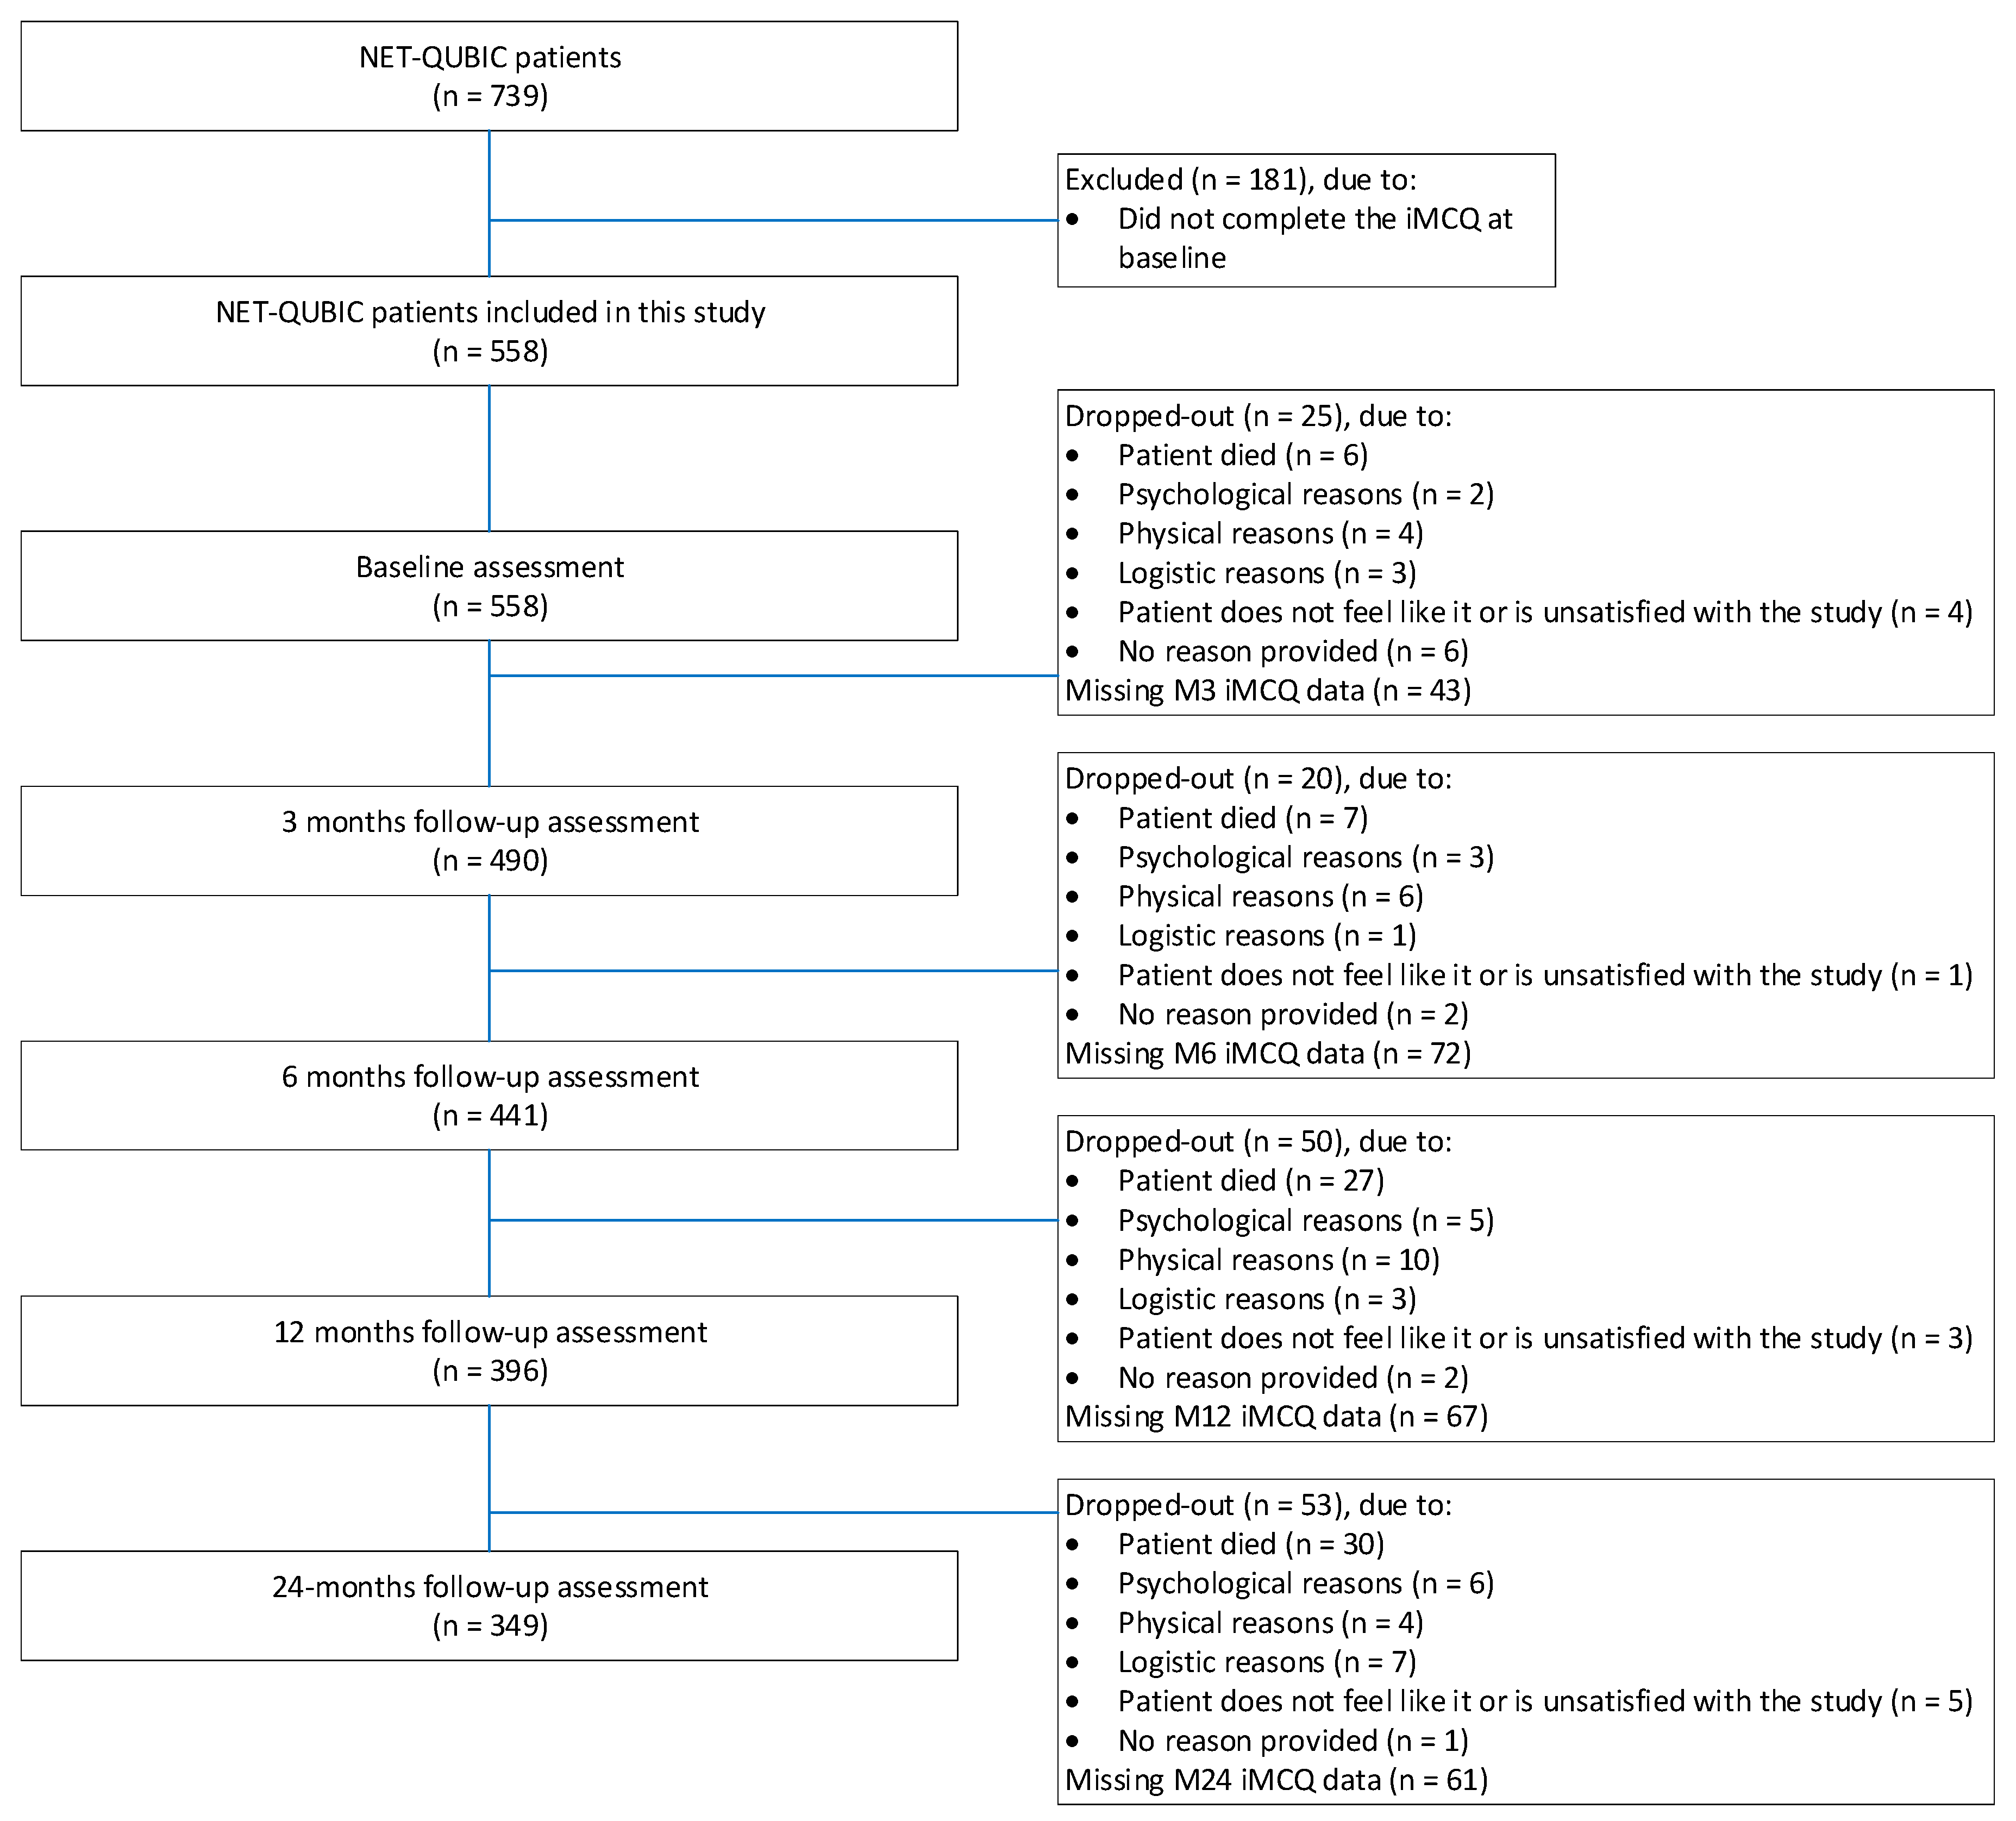
Of the 739 eligible patients, 181 patients (25%) did not fill in the iMCQ at baseline, resulting in a study population of 558 patients. Patients who were included in this specific study often lived with others, were more often diagnosed with tumor stage I or II, and often had a better WHO performance state and less comorbidity, compared to those who were not included (p < 0.05).
The characteristics of the study population are shown in Table 1. The majority were male (74%) and the mean age was 64 years (range 19–86 years). Most patients had a stage III–IV tumor (57%). The tumors were most often located in the oropharynx (36%), followed by an oral cavity (28%), larynx (27%), hypopharynx (6%), and unknown primary (3%). Approximately one third of the patients (33%) were treated with radiotherapy, 21% of the patients were treated with surgery, and 45% of the patients were treated with a combination of treatment modalities (chemoradiation, or surgery and (chemo)radiotherapy). In total, 88% of all 558 patients included in this study completed at least one follow-up measure (Figure 1). Reasons for drop-out are shown in Figure 1. More detailed information on the study flow is provided in a previous published study [30].
Table 1.
Characteristics of included and excluded patients.
Figure 1.
Medical consumption questionnaire (iMCQ).
The prevalence rate of a high level of distress was 33% at baseline, and 17% at 12-month follow-up. The prevalence rate of symptoms of anxiety was 26% at baseline and 9% at 12-month follow-up, and of symptoms of depression was 14% at baseline and 9% at 12-month follow-up. FCR was found in 37% of the patients at baseline and 29% at 12-month follow-up. The prevalence rates of anxiety and depression disorders were substantially lower; 2% and 3% at baseline and 1% and 6% at 12-month follow-up, respectively.
3.2. Use of Healthcare and Informal Care
Frequencies of healthcare and informal care use are presented in Table 2. Use of mental healthcare was relatively low at all time points (<9%). Use of primary care ranged from 92% at baseline to 57–59% at 12- and 24-month follow-up. Use of supportive care ranged from 54–80%, of which physical therapy, dietician care, and oral hygiene care were used most often, and social work and support groups were used less often (<5%). The use of informal care ranged from 9–24%.
Table 2.
Use of care at baseline, 3-, 6-, 12-, and 24-month follow-up.
Patients who used mental healthcare and primary care reported, on average, three to four visits in the previous 3 months. Patients who used supportive care reported, on average, four to nine visits, and patients who used informal care received, on average, between 29 and 58 h of care in the last 3 months.
3.3. Psychological Problems in Relation to Use of Healthcare and Informal Care
Results of univariate analyses testing psychological problems in relation to healthcare and informal care use are shown in Appendix A and Appendix B. Psychological problems that were significantly associated with care use in the univariate models were further analyzed in multivariate analyses with correction for potential confounders (Table 3); this excludes the associations with mental healthcare use, as a consequence of low mental healthcare use. Distress, symptoms of anxiety, symptoms of depression, FCR, anxiety disorder, and depression disorder were significantly associated with higher mental healthcare use for at least one time point. Use of mental healthcare ranged from 3% to 7% among patients without psychological problems, and from 6% to 50% among patients with psychological problems (Appendix A and Appendix B). Anxiety disorder at 12-month follow-up in relation to care use could not be analyzed due to an insufficient sample size (i.e., <10 patients with an anxiety disorder at 12-month follow-up).
Table 3.
Multivariate analyses testing associations between psychological problems at baseline and 12- months follow-up and use of care at baseline, 3-,6-,12-, and 24-month follow-up.
3.4. Psychological Problems in Relation to Costs
Results of the analyses regarding associations between psychological problems at baseline, and costs at baseline, 3-, 6-, 12-, and 24-month follow-up, adjusted for sociodemographic and clinical factors, are shown in Table 4. Psychological distress, symptoms of anxiety, and FCR at baseline were significantly associated with higher costs in the 3 months before baseline assessment (probability >98.3%). Patients with distress at baseline had, on average, €93 (BCa 95% CI = €18; €180) higher costs at baseline, patients with symptoms of anxiety at baseline had, on average, €125 (BCa 95% CI = €45; €231) higher costs at baseline, and patients with FCR at baseline had, on average, €80 (BCa 95% CI = €10; €162) higher costs at baseline, compared to patients without these psychological problems.
Table 4.
Differences in costs at baseline, 3-,6-,12-, and 24-month follow-up between patients with and without psychological problems at baseline and 12-months follow-up.
Results of the analyses for the associations between psychological problems at 12-month follow-up, and costs at 12- and 24-month follow-up, adjusted for sociodemographic and clinical factors, are shown in Table 4. None of the associations were statistically significant. However, the probability approach showed that the probability that anxiety disorder at baseline was associated with higher costs at 6-month follow-up was high (probability of 89.3%). Furthermore, the probability that depression disorder at baseline was associated with higher costs at 3-, 6-, and 12-month follow-up, and that depression disorder at 12-month follow-up was associated with higher costs at 24-month follow-up, was high (probability between 89.6% and 95.1%). On the other hand, the probability that depression disorder at baseline was associated with higher costs at 24-month follow-up was low (probability of 5.2%).
4. Discussion
The aim of this study was to investigate the relationship between psychological problems and use of care and costs from baseline up to 2 years after treatment among HNC patients. Overall, the results of this study support the suggestion posed by Carlson and Bultz [13] that cancer patients with psychological problems not only make more use of mental healthcare, but also other types of healthcare. The results are also in line with the general findings of a systematic review that cancer patients with psychological problems make more use of mental and primary healthcare, and have higher healthcare costs [14].
In this exploratory prospective study, we specifically investigated the relationship between various types of psychological problems (distress, symptoms of anxiety and depression, FCR, and anxiety and depression disorder) and various types of care (mental, primary, supportive, and informal care) and costs. We found that HNC patients with distress, symptoms of anxiety, or FCR at time of diagnosis had significantly more costs in the 3 months prior to diagnosis. It was also highly likely that patients with psychological problems at baseline had more costs compared to patients without psychological problems at 3- (depression disorder), 6- (anxiety and depression disorder), and 12- (depression disorder) month follow-up, and that patients with psychological problems 12 months after treatment had higher costs at 12- (distress) and 24- (depression disorder) month follow-up. In addition, patients with symptoms of anxiety at baseline made more use of primary care and supportive care, and patients with FCR or an anxiety disorder used informal care more often, 3 months after treatment. Patients with symptoms of depression at baseline made more use of informal care 6 months after treatment, and patients who had distress, symptoms of anxiety, or FCR more often made use of primary care at 12-month follow-up. Patients with symptoms of anxiety at 12-month follow-up made more use of primary care at that assessment time. Two years after treatment, patients with psychological problems at baseline or 12-month follow-up did not seem to make use of primary care as often, but made more use of supportive care (patients with distress or symptoms of anxiety at baseline, and patients with FCR at 12-month follow-up) and informal care (patients with a depression disorder at 12-month follow-up).
The costs among patients with psychological problems before treatment and/or 12 months after treatment were, when likely to be more expensive (i.e., probability >89%), on average between €80 and €391 higher during a 3-month time period compared to patients without these psychological problems. Other studies reported that cancer patients with a depression disorder or anxiety disorder had, on average, between $6000 to $25,000 and $15,000 to $60,000 higher costs, respectively, in a year [17,31,32,33]. A reason for this cost difference might be that, in our study, only costs related to mental, primary, supportive and informal care were included, whereas in these other studies, additional costs of inpatient, outpatient, and emergency room visits were included. Another explanation may be that these other studies focused on psychiatric disorders, and increased care use and costs are especially prevalent among those with psychiatric disorders.
An explanation for the higher costs among patients with psychological symptoms or disorders may be that patients with a poorer clinical status (comorbidity, more advanced cancer stage) are more likely to develop psychological symptoms or a psychiatric disorder [7,34]. Therefore, higher healthcare use among those with psychological symptoms/disorders might not be a result of psychological symptoms/disorder, but instead be a result of a poorer clinical status. To account for this, we adjusted for confounders at baseline, such as cancer stage, treatment modalities, and comorbidity. Although some associations were no longer significant after adjustment, several associations remained significant, indicating that associations between psychological problems and healthcare use and costs do not (entirely) result from worse clinical outcomes.
Other explanations for higher care use and costs among those with psychological symptoms or disorders, as previously hypothesized by Carlson and Bultz [13], are that patients with psychological problems may be less likely to fully adhere to medical treatment, and that they are less likely to maintain a healthy lifestyle; these factors may lead to decreased overall health at follow-up, and, consequently, an increased need for and use of healthcare services. Surprisingly, results at 24-month follow-up suggest that patients with psychological problems at baseline have lower costs. An explanation for this may be that the association between psychological problems and costs is especially present at short-term follow-up, and that later on, other factors become more important in the association with costs. In the current study, it seems that patients with a psychiatric disorder made solely more use of informal care (and not professional primary or supportive care), whereas patients with distress, symptoms of anxiety or depression, or FCR made more use of professional care (i.e., primary care and supportive care). Due to limited power, the use of mental healthcare could not be investigated via multivariate models. However, univariate analyses showed that mental healthcare was used relatively more often by patients with a psychiatric disorder (mental health care was used by up to 40% of patients with a disorder at baseline versus 16% among patients with psychological symptoms). This suggests that patients with a psychiatric disorder are more likely to be referred to mental healthcare, whereas patients with psychological symptoms may be more likely to be referred to supportive care, or to consult their general practitioner. Another observation is that, seemingly, patients with symptoms of depression, or a depression disorder, made more use of informal care, whereas patients with symptoms of anxiety, FCR, or an anxiety disorder, made more use of both primary care and informal care. An explanation for this may be that anxious patients visit healthcare providers more often to be reassured that their health is under control.
To unravel these potential differences, further research is needed on the course of healthcare utilization after diagnosis, and the moderation or mediating effects of psychological problems, cancer recurrence, lifestyle behavior, and treatment adherence. The use of mental healthcare in this study population was low, which may be related to suboptimal organization of care and/or willingness to accept mental healthcare by patients. Brebach et al. [35] estimated that 60% of cancer patients with distress, anxiety, or depression accept psychological treatment when offered [35]. This percentage was also reported in a recent study among mixed cancer patients with adjustment disorders [36]. Further research is needed on factors that may explain why some patients receive psychological care in clinical practice and some do not, including the role of the patient him/herself (e.g., coping style, a self-perceived need for psychological care).
A key strength of this study is the longitudinal design, which enabled prospective analyses of associations between psychological problems and care use and costs. Another strength of this study is that patient-reported outcomes and diagnostic interviews were used to identify patients with psychological symptoms and patients with an anxiety or depression disorder, respectively. Previous studies used health insurance data [17,18] derived from routine care; however, it is known that psychological symptoms and psychiatric disorders often remain undiagnosed among cancer patients [37]. This may have resulted in an underestimation of the cost difference. Additionally, in the current study, we controlled for sociodemographic and clinical confounders. A potential limitation of this study is the large number of analyses performed. We did not perform a Bonferroni assessment, as different psychological problems were investigated in relation to different types of healthcare use [38]. Moreover, sample size was too small to conduct multivariate analyses with respect to mental healthcare use. The small number of patients with an anxiety or depression disorder necessitates caution in interpreting the results. Furthermore, it would be interesting to include medication use in the analysis. Unfortunately, these data are not yet available.
Finally, this study investigated the associations between psychological problems and care use and costs among Dutch cancer patients. Use of care may be limited or driven by health insurance systems [39].
5. Conclusions
HNC patients with psychological problems more often use healthcare and informal care, and have higher costs. This association remained after adjusting for demographic and clinical characteristics, indicating that the association does not result from worse clinical outcomes in patients with psychological problems.
Author Contributions
Conceptualization, F.E.v.B., F.J. and I.M.V.-d.L.; Data curation, F.J.; Formal analysis, F.E.v.B., F.J. and B.I.L.-W.; Investigation, R.J.B.d.J., J.A.L., C.R.L., J.H.S., R.P.T., C.H.J.T. and I.M.V.-d.L.; Methodology, F.E.v.B., F.J. and B.I.L.-W.; Supervision, I.M.V.-d.L.; Writing—original draft, F.E.v.B., F.J. and I.M.V.-d.L.; Writing—review & editing, R.J.B.d.J., J.A.L., C.R.L., J.H.S., R.P.T., C.H.J.T., J.A.E.C., J.B.P., B.I.L.-W. and I.M.V.-d.L. All authors have read and agreed to the published version of the manuscript.
Funding
This study was carried out using the research infrastructure within The Netherlands Quality of life and Biomedical Cohort study in head and neck cancer (NET-QUBIC) project funded by the Dutch Cancer Society (grant number VU 2013–5930) and the Dutch Cancer Society, Alpe Young Investigator Grant [grant number 12820]. The funding body had no role in the study design, the data collection, analysis, interpretation, or the manuscript preparation.
Institutional Review Board Statement
The study was conducted in accordance with the Declaration of Helsinki, and approved by the Institutional Review Board of the coordinating research center (Amsterdam UMC (location VUmc)) (2013.301 (A2018.307)-NL45051.029.13).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study.
Data Availability Statement
The datasets generated and analyzed during the current study are not publicly available as the collection and integration of large amounts of personal, biological, genetic and diagnostic information precludes open access to the NET-QUBIC research data. Data are available from the corresponding author on reasonable request. On the NET-QUBIC website (www.kubusproject.nl) is described how NET-QUBIC data are made available for the research community.
Conflicts of Interest
The authors declare no conflict of interest.
Appendix A
Table A1.
Psychological problems at baseline in relation to healthcare use at baseline, 3-, 6-, 12-, and 24-month follow-up.
Appendix B
Table A2.
Psychological problems at 12-month follow-up in relation to healthcare use at baseline, 12-, and 24-month follow-up.
References
- Buchmann, L.; Ashby, S.; Cannon, R.B.; Hunt, J.P. Psychosocial distress in patients with thyroid cancer. Otolaryngol. -Head Neck Surg. 2015, 152, 644–649. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Deng, Y.T.; Zhong, W.N.; Jiang, Y. Measurement of distress and its alteration during treatment in patients with nasopharyngeal carcinoma. Head Neck 2014, 36, 1077–1086. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lewis, S.; Pandey, S.; Salins, N.; Deodhar, J.; Patil, V.; Gupta, T.; Laskar, S.G.; Budrukkar, A.; Murthy, V.; Joshi, A.; et al. Distress Screening in Head and Neck Cancer Patients Planned for Cancer-Directed Radiotherapy. Laryngoscope 2021, 131, 2023–2029. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Neilson, K.; Pollard, A.; Boonzaier, A.; Corry, J.; Castle, D.; Smith, D.; Trauer, T.; Couper, J. A longitudinal study of distress (depression and anxiety) up to 18 months after radiotherapy for head and neck cancer. Psycho-Oncology 2013, 22, 1843–1848. [Google Scholar] [CrossRef] [Scilit]
- Van Beek, F.; Jansen, F.; Mak, L.; Lissenberg-Witte, B.; Buter, J.; Vergeer, M.; Voortman, J.; Cuijpers, P.; Leemans, C.; Verdonck-de Leeuw, I. The course of symptoms of anxiety and depression from time of diagnosis up to 2 years follow-up in head and neck cancer patients treated with primary (chemo) radiation. Oral Oncol. 2020, 102, 104576. [Google Scholar] [CrossRef] [Scilit]
- Wu, Y.-S.; Lin, P.-Y.; Chien, C.-Y.; Fang, F.-M.; Chiu, N.-M.; Hung, C.-F.; Lee, Y.; Chong, M.-Y. Anxiety and depression in patients with head and neck cancer: 6-month follow-up study. Neuropsychiatr. Dis. Treat. 2016, 12, 1029. [Google Scholar] [CrossRef] [Scilit]
- Hammerlid, E.; Ahlner-Elmqvist, M.; Bjordal, K.; Biörklund, A.; Evensen, J.; Boysen, M.; Jannert, M.; Kaasa, S.; Sullivan, M.; Westin, T. A prospective multicentre study in Sweden and Norway of mental distress and psychiatric morbidity in head and neck cancer patients. Br. J. Cancer 1999, 80, 766–774. [Google Scholar] [CrossRef] [Scilit]
- Hammerlid, E.; Silander, E.; Hörnestam, L.; Sullivan, M. Health-related quality of life three years after diagnosis of head and neck cancer—a longitudinal study. Head Neck J. Sci. Spec. Head Neck 2001, 23, 113–125. [Google Scholar] [CrossRef] [Scilit]
- Lydiatt, W.M.; Moran, J.; Burke, W.J. A review of depression in the head and neck cancer patient. Clin. Adv. Hematol. Oncol. 2009, 7, 397–403. [Google Scholar]
- Mehnert, A.; Brähler, E.; Faller, H.; Härter, M.; Keller, M.; Schulz, H.; Wegscheider, K.; Weis, J.; Boehncke, A.; Hund, B. Four-week prevalence of mental disorders in patients with cancer across major tumor entities. J. Clin. Oncol. 2014, 32, 3540–3546. [Google Scholar] [CrossRef] [Scilit]
- Mirosevic, S.; Thewes, B.; van Herpen, C.; Kaanders, J.; Merkx, T.; Humphris, G.; Baatenburg de Jong, R.J.; Langendijk, J.A.; Leemans, C.R.; Terhaard, C.H. Prevalence and clinical and psychological correlates of high fear of cancer recurrence in patients newly diagnosed with head and neck cancer. Head Neck 2019, 41, 3187–3200. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dunne, S.; Mooney, O.; Coffey, L.; Sharp, L.; Desmond, D.; Timon, C.; O’Sullivan, E.; Gallagher, P. Psychological variables associated with quality of life following primary treatment for head and neck cancer: A systematic review of the literature from 2004 to 2015. Psycho-Oncology 2017, 26, 149–160. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carlson, L.E.; Bultz, B.D. Efficacy and medical cost offset of psychosocial interventions in cancer care: Making the case for economic analyses. Psycho-Oncol. J. Psychol. Soc. Behav. Dimens. Cancer 2004, 13, 837–849. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Van Beek, F.E.; Wijnhoven, L.M.; Holtmaat, K.; Custers, J.A.; Prins, J.B.; Verdonck-de Leeuw, I.M.; Jansen, F. Psychological problems among cancer patients in relation to healthcare and societal costs: A systematic review. Psycho-Oncology 2021, 30, 1801–1835. [Google Scholar] [CrossRef] [Scilit]
- Williams, J.T.W.; Pearce, A. A systematic review of fear of cancer recurrence related healthcare use and intervention cost-effectiveness. Psycho-Oncology 2021, 30, 1185–1195. [Google Scholar] [CrossRef] [Scilit]
- Kuhnt, S.; Brähler, E.; Faller, H.; Härter, M.; Keller, M.; Schulz, H.; Wegscheider, K.; Weis, J.; Boehncke, A.; Hund, B. Twelve-month and lifetime prevalence of mental disorders in cancer patients. Psychother. Psychosom. 2016, 85, 289–296. [Google Scholar] [CrossRef] [Scilit]
- Jeffery, D.D.; Art Ambrosio, L.; Hopkins, L.; Burke, H.B. Mental health comorbidities and cost/utilization outcomes in head and neck cancer patients. J. Psychosoc. Oncol. 2019, 37, 301–318. [Google Scholar] [CrossRef] [Scilit]
- Laurence, B.; Mould-Millman, N.K.; Nero Jr, K.E.; Salter, R.O.; Sagoo, P.K. Depression and hospital admission in older patients with head and neck cancer: Analysis of a national healthcare database. Gerodontology 2017, 34, 284–287. [Google Scholar] [CrossRef] [Scilit]
- Verdonck-de Leeuw, I.; Jansen, F.; Brakenhoff, R.; Langendijk, J.; Takes, R.; Terhaard, C.; de Jong, R.B.; Smit, J.; Leemans, C. Advancing interdisciplinary research in head and neck cancer through a multicenter longitudinal prospective cohort study: The NETherlands QUality of life and BIomedical Cohort (NET-QUBIC) data warehouse and biobank. BMC Cancer 2019, 19, 765. [Google Scholar]
- Paleri, V.; Wight, R. Applicability of the adult comorbidity evaluation–27 and the Charlson indexes to assess comorbidity by notes extraction in a cohort of United Kingdom patients with head and neck cancer: A retrospective study. J. Laryngol. Otol. 2002, 116, 200–205. [Google Scholar] [CrossRef] [Scilit]
- Spinhoven, P.; Ormel, J.; Sloekers, P.; Kempen, G.; Speckens, A.E.; van Hemert, A.M. A validation study of the Hospital Anxiety and Depression Scale (HADS) in different groups of Dutch subjects. Psychol. Med. 1997, 27, 363–370. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Custers, J.A.; van den Berg, S.W.; van Laarhoven, H.W.; Bleiker, E.M.; Gielissen, M.F.; Prins, J.B. The cancer worry scale: Detecting fear of recurrence in breast cancer survivors. Cancer Nurs. 2014, 37, E44–E50. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Custers, J.A.; Gielissen, M.F.; Janssen, S.H.; de Wilt, J.H.; Prins, J.B. Fear of cancer recurrence in colorectal cancer survivors. Support. Care Cancer 2016, 24, 555–562. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van de Wal, M.; van Oort, I.; Schouten, J.; Thewes, B.; Gielissen, M.; Prins, J. Fear of cancer recurrence in prostate cancer survivors. Acta Oncol. 2016, 55, 821–827. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wittchen, H.-U. Reliability and validity studies of the WHO-Composite International Diagnostic Interview (CIDI): A critical review. J. Psychiatr. Res. 1994, 28, 57–84. [Google Scholar] [CrossRef] [Scilit]
- Bouwmans, C.; Hakkaart-van Rooijen, L.; Koopmanschap, M.; Krol, M.; Severens, H.; Brouwer, W. Guideline iMTA Medical Consumption Questionnaire; iMTA, Erasmus Universiteit: Rotterdam, The Netherlands, 2013. [Google Scholar]
- Bouwmans, C.; Krol, M.; Severens, H.; Koopmanschap, M.; Brouwer, W.; Hakkaart-van Roijen, L. The iMTA productivity cost questionnaire: A standardized instrument for measuring and valuing health-related productivity losses. Value Health 2015, 18, 753–758. [Google Scholar] [CrossRef] [Scilit]
- Hakkaart-Van Rooijen, L.; Tan, S.; Bouwmans, C. Handleiding voor Kostenonderzoek, Methoden en Standaardprijzen voor Ecenomische Valuaties in de Gezondheidszorg; Erasmus Universiteit Rotterdam: Rotterdam, The Netherlands, 2010. [Google Scholar]
- Elliot, R.; Payne, K. Statistical handling of data in economic analysis. In Essentials of Economic Evaluation in Healthcare; Pharmaceutical Press: London, UK, 2005; pp. 185–202. [Google Scholar]
- Jansen, F.; Brakenhoff, R.H.; Baatenburg de Jong, R.J.; Langendijk, J.A.; Leemans, C.R.; Takes, R.P.; Terhaard, C.H.; Smit, J.H.; Verdonck-de Leeuw, I.M. Study retention and attrition in a longitudinal cohort study including patient-reported outcomes, fieldwork and biobank samples: Results of the Netherlands quality of life and Biomedical cohort study (NET-QUBIC) among 739 head and neck cancer patients and 262 informal caregivers. BMC Med. Res. Methodol. 2022, 22, 27. [Google Scholar]
- Pan, X.; Sambamoorthi, U. Health care expenditures associated with depression in adults with cancer. J. Community Support. Oncol. 2015, 13, 240. [Google Scholar] [CrossRef] [Scilit]
- Boele, F.W.; Meads, D.; Jansen, F.; Verdonck-de Leeuw, I.M.; Heimans, J.J.; Reijneveld, J.C.; Short, S.C.; Klein, M. Healthcare utilization and productivity loss in glioma patients and family caregivers: The impact of treatable psychological symptoms. J. Neuro.-Oncol. 2020, 147, 485. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mausbach, B.T.; Decastro, G.; Schwab, R.B.; Tiamson-Kassab, M.; Irwin, S.A. Healthcare use and costs in adult cancer patients with anxiety and depression. Depress. Anxiety 2020, 37, 908–915. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Leeuw, J.R.J.; de Graeff, A.; Ros, W.J.; Blijham, G.H.; Hordijk, G.J.; Winnubst, J.A. Prediction of depression 6 months to 3 years after treatment of head and neck cancer. Head Neck J. Sci. Spec. Head Neck 2001, 23, 892–898. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Brebach, R.; Sharpe, L.; Costa, D.S.; Rhodes, P.; Butow, P. Psychological intervention targeting distress for cancer patients: A meta-analytic study investigating uptake and adherence. Psycho-Oncology 2016, 25, 882–890. [Google Scholar] [CrossRef] [Scilit]
- Van Beek, F.; Wijnhoven, L.; Custers, J.; Holtmaat, K.; De Rooij, B.; Horevoorts, N.; Aukema, E.; Verheul, S.; Eerenstein, S.; Strobbe, L. Adjustment disorder in cancer patients after treatment: Prevalence and acceptance of psychological treatment. Support. Care Cancer 2021, 30, 1797–1806. [Google Scholar] [CrossRef] [Scilit]
- Kissane, D.W. Unrecognised and untreated depression in cancer care. Lancet. Psychiatry 2014, 1, 320–321. [Google Scholar] [CrossRef] [Scilit]
- Armstrong, R.A. When to use the Bonferroni correction. Ophthalmic Physiol. Opt. 2014, 34, 502–508. [Google Scholar] [CrossRef] [Scilit]
- Walker, E.R.; Cummings, J.R.; Hockenberry, J.M.; Druss, B.G. Insurance status, use of mental health services, and unmet need for mental health care in the United States. Psychiatr. Serv. 2015, 66, 578–584. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).