Epicardial Adipose Tissue in Diabetic Heart Disease: Impact on Cardiac Function and Modulation Strategies, a Comprehensive Review
 , , , , , ,

Abstract
1. Introduction
1.1. EAT’s Distinctive Metabolic Profile
1.2. EAT’s Physiologic Role and Its Pathologic Transformation
1.3. Literature Search
2. Excessive EAT-Related Disease
2.1. Obesity
2.2. T2DM
2.3. CAD
2.4. AF
2.5. VT
3. Diabetic Heart Disease
3.1. Diabetic Myocardial Disorder
3.2. Diabetic Pericardial Disorder
4. EAT’s Impact on Myocardial Function
4.1. EAT’s Impact Primarily on Systolic Heart Disease
4.2. EAT’s Impact Primarily on Diastolic Heart Disease
5. Non-Pharmacological Modulation of EAT
5.1. Body Weight Control
5.2. Diet
5.3. Physical Activity
5.4. Smoking Cessation
5.5. Hypoxic Burden Control
6. Pharmacological EAT Modulation in Diabetes
6.1. Overview of Antidiabetic Therapy and EAT
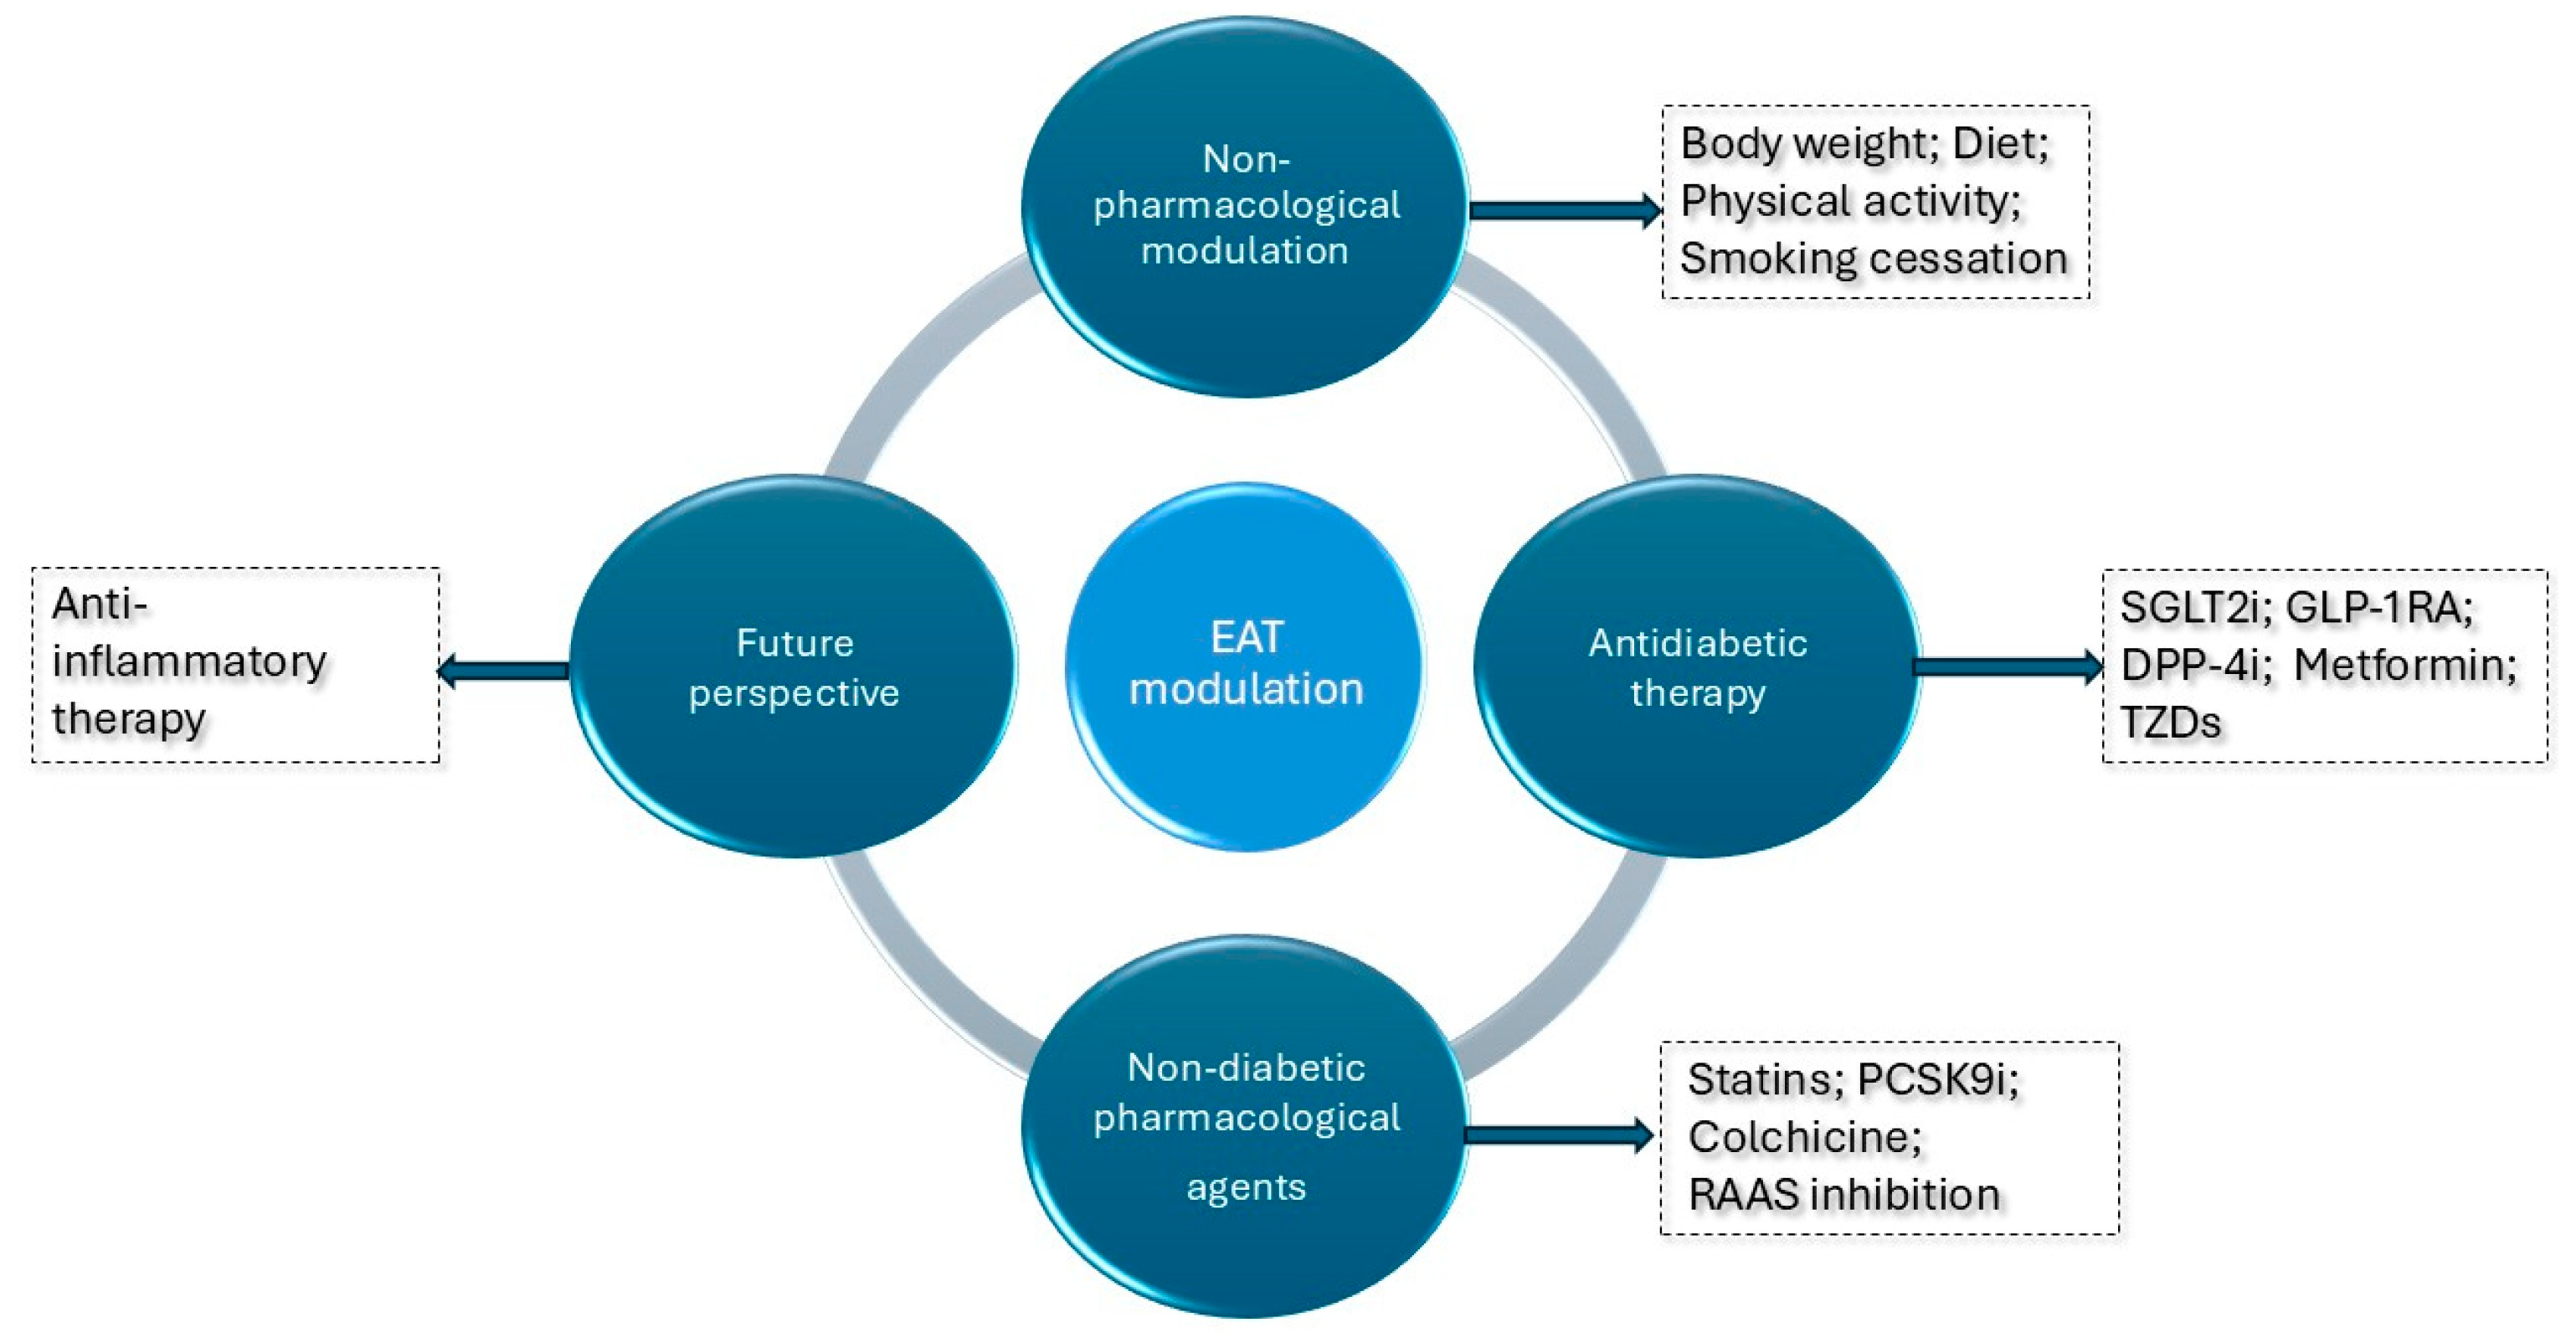
- Metformin, a biguanide, has long been regarded as the first-line therapy for type 2 diabetes, in conjunction with dietary modification, weight reduction, and regular physical activity. Its primary mechanisms include suppression of hepatic glucose production through inhibition of gluconeogenesis and glycogenolysis, along with improved peripheral insulin sensitivity. As monotherapy, metformin exerts a potent glucose-lowering effect in a dose-dependent manner, with a low risk of hypoglycemia. Dose adjustment is required in accordance with renal function, and its use is contraindicated in patients with a glomerular filtration rate below 30 mL/min/1.73 m2, as well as in diabetic ketoacidosis, conditions associated with tissue hypoxia, and hepatic insufficiency [110,111]. Metformin has been shown to significantly reduce EAT thickness. Clinical studies report that 3 months of metformin monotherapy decreases EAT in both newly diagnosed T2DM patients and obese children with insulin resistance [112,113]. Beyond structural changes, metformin also influences EAT-related cardiac risk. Since EAT contributes to AF development, its reduction is clinically relevant. In parallel, metformin improves atrial electromechanical delay—a predictor of arrhythmias—suggesting a protective electrophysiological effect [113].
- 2.
- Thiazolidinediones (glitazones; TZDs) are oral antidiabetic agents that enhance insulin sensitivity in the liver, adipose tissue, and skeletal muscle via activation of the nuclear transcription factor PPAR-γ. They also reduce hepatic glucose production and provide effective glycemic control without significantly increasing the risk of hypoglycemia. Although beneficial effects on CV outcomes have been observed in patients with macrovascular complications, their use may be associated with adverse effects such as congestive HF [121]. TZDs are associated with weight gain, raising concerns about their impact on EAT [122]. However, their effect appears to involve fat redistribution rather than simple accumulation. TZDs promote a shift from visceral fat (including EAT) to SAT [123]. Pioglitazone has been shown to reduce EAT thickness despite increasing overall body weight [124]. While it may increase pericardial fat volume, this change does not appear to impair myocardial function over short-term follow-up and may even improve diastolic function in patients with T2DM [125]. Additionally, pioglitazone exerts anti-inflammatory effects by suppressing inflammatory gene expression in EAT, particularly in patients with atherosclerosis [126]. Rosiglitazone demonstrates distinct metabolic effects, including rapid induction of EAT browning in experimental animal models characterized by increased expression of thermogenic and fatty acid oxidation genes. This shift enhances lipid turnover and contributes to its hypolipidemic action [127]. Despite this, its clinical use is limited by an increased risk of myocardial infarction [128]. Taken together, TZDs may have beneficial effects on EAT distribution, function, and inflammatory activity, although their net CV impact remains uncertain.
- 3.
- Dipeptidyl peptidase-4 (DPP-4) inhibitors act by preventing the degradation of endogenous incretin hormones, including glucagon-like peptide-1 (GLP-1) and gastric inhibitory peptide (GIP). By increasing circulating levels of active incretins, they enhance glucose-dependent insulin secretion and suppress glucagon release, resulting in a very low risk of hypoglycemia. Their glucose-lowering efficacy is moderate, and they are generally well tolerated. Large CV outcome trials (CVOTs) have demonstrated no significant differences in CV risk compared with placebo for this class of agents, with the exception of an increased incidence of hospitalization for HF observed with saxagliptin (3.5% vs. 2.8%) [129,130]. Regarding EAT, sitagliptin has been shown to rapidly reduce its thickness, an effect that appears independent of changes in BMI and glycemia, suggesting additional mechanisms beyond glycemic and lipid-lowering actions [131]. Comparative data indicate that its effects on fat accumulation, cardiac function, and myocardial fatty acid metabolism are similar to those of empagliflozin [132]. However, experimental evidence on DPP-4 inhibition and cardiac remodeling remains inconsistent. Some studies report reduced myocardial fibrosis via decreased collagen type III production, while others show exacerbation of fibrosis, inflammation, and impaired ventricular function [133,134]. Although these findings do not directly address EAT, it is plausible that EAT may contribute to mediating the cardiac effects of DPP-4 inhibitors.
- 4.
- Glucagon-like peptide-1 receptor agonists (GLP-1 RA; mimetics and analogs) bind to and activate the GLP-1 receptor, thereby enhancing glucose-dependent insulin secretion without causing significant hypoglycemia. They also modestly delay gastric emptying, which slows postprandial glucose absorption. These agents are typically administered subcutaneously, although oral formulations of semaglutide are available. Their resistance to degradation by the DPP-4 enzyme results in a prolonged half-life. GLP-1 RAs provide moderate to substantial reductions in HbA1c and are associated with weight loss. Meta-analyses of clinical trials indicate that they reduce the risk of major CV events in patients with T2DM and established atherosclerotic CV disease [104,135]. EAT has emerged as a relevant therapeutic target of GLP-1 RA, as it expresses GLP-1 receptors at higher levels than SAT, enabling direct drug effects independent of glycemic control [136]. The presence of GLP-1 receptors on cardiomyocytes further supports the pleiotropic CV actions of this drug class [137]. Clinical studies consistently demonstrate that GLP-1 RAs significantly reduce EAT thickness and volume, with reductions of approximately 20–30% after 3 months of therapy and up to 40% within 12–24 weeks, suggesting a class effect with dose dependency [120,138,139]. Meta-analytic data indicate that GLP-1 RAs exert a greater early impact on EAT reduction compared with other cardiometabolic agents, such as SGLT2 inhibitors and statins, although effects may become comparable with SGLT2 inhibitors over longer treatment durations. The magnitude of EAT reduction appears greater in younger individuals and those with higher BMI [140]. Mechanistically, GLP-1 receptor activation in EAT is associated with enhanced fatty acid β-oxidation and promotion of white-to-brown adipose tissue differentiation, supported by the upregulation of brown adipose tissue–related genes [141]. Additionally, GLP-1 RAs improve the metabolic and inflammatory profile of EAT by reducing triglyceride and low-density lipoprotein content, as well as systemic inflammatory and oxidative stress markers [142]. These changes are accompanied by improvements in vascular stiffness and cardiac function, indicating a link between EAT modulation and CV benefit [143,144]. Emerging dual incretin therapies, such as tirzepatide, may further expand this therapeutic paradigm due to combined GLP-1 and GIP receptor activity, although current evidence regarding their direct effects on EAT remains limited [83].
- 5.
- Sodium–glucose cotransporters: The kidneys play a crucial role in glucose homeostasis through reabsorption mediated by sodium–glucose cotransporters 1 and 2 (SGLT-1 and SGLT-2) [145]. Inhibitors of these transporters represent the newest class of oral antidiabetic agents and act by increasing urinary glucose excretion through lowering the renal threshold for glucose (in comparison to other medications that primarily work to utilize glucose). Large CVOTs have shown that SGLT2 inhibitors (SGLT2i) confer CV protection and reduce hospitalization for HF within weeks of initiation, regardless of baseline CV risk, and demonstrate a class effect. These findings suggest that mechanisms beyond glycemic control and atherogenesis may underlie their cardioprotective effects [146]. Emerging evidence suggests that SGLT-2i may exert cardioprotective effects partly through modulation of EAT. Experimental and clinical studies indicate that these agents reduce EAT, alter its metabolic activity, and attenuate its inflammatory profile, thereby potentially contributing to improved CV outcomes. Cinti et al. demonstrated that dapagliflozin induced a rapid reduction in epicardial fat thickness of approximately 19% within four weeks in patients with T2DM, with a more pronounced effect on EAT compared to other adipose depots, likely reflecting its higher metabolic activity [147]. However, these findings should be interpreted cautiously due to the small sample size. The work by Díaz-Rodríguez et al. showed that dapagliflozin increased glucose uptake in human EAT samples via glucose transporter 4 (GLUT4), suggesting a more complex and context-dependent metabolic effect [148]. Nevertheless, further mechanistic support comes from the study of Sato et al., who reported that dapagliflozin significantly decreased EAT at the 6-month follow-up compared with the conventionally treated patients with T2DM and CAD. Decrease in EAT volume was accompanied by reduction in TNF-α level and body weight [149]. Clinical data in non-diabetic patients with heart failure with reduced ejection fraction (HFrEF) further support the beneficial effects of SGLT-2 inhibition. Requena-Ibáñez et al. reported that empagliflozin significantly reduced epicardial fat volume and was associated with decreased interstitial myocardial fibrosis and improved aortic stiffness, with fibrosis assessed indirectly via extracellular volume fraction as a validated prognostic marker in HF. Comparative analyses of cardiometabolic therapies have produced mixed findings. Although in the previously mentioned study of Myasoedova et al. it was reported that GLP-1RA may be more effective than SGLT-2i in reducing EAT, Bao et al. suggested superiority of SGLT-2 inhibitors over GLP-1RA and exercise interventions in reducing EAT, highlighting ongoing uncertainty regarding the most effective pharmacological strategy [140,150]. Collectively, SGLT-2 inhibitors may improve CV outcomes by restoring the balance between pro- and anti-inflammatory adipokines, thereby influencing insulin resistance, atherosclerosis, coagulation, and fibrinolysis [151,152]. They have been shown to modulate adipokine secretion, including reductions in leptin and increases in adiponectin, as well as to improve adipocyte differentiation and reduce inflammatory cytokine release [153]. Reduced EAT volume and inflammation may contribute to decreased risk of HF, AF, and CAD, as well as prevention of adverse cardiac remodeling. Even so, limited mechanistic understanding of SGLT2 inhibitors’ mode of action underscores the need for further research in this area.
- 6.
- Sulfonylureas stimulate insulin secretion from pancreatic β-cells independently of plasma glucose levels, meaning they act in hyperglycemic, normoglycemic, and even hypoglycemic states. They are among the most potent oral agents for lowering blood glucose [154]. Some observational studies and meta-analyses have suggested a potential association between certain first-generation sulfonylureas, such as glibenclamide, and increased CV mortality. Still, this finding has not been consistently confirmed in randomized controlled trials [155].
- 7.
- Glinides are short-acting insulin secretagogues that, like sulfonylureas, stimulate insulin release from pancreatic β-cells. Their rapid onset and short duration of action necessitate administration immediately before meals, often requiring multiple daily doses. The risk of hypoglycemia is somewhat lower compared to sulfonylureas [156]. No data are available regarding their effects on EAT.
- 8.
- Insulin is an endocrine peptide hormone that interacts with plasma membrane-bound receptors on target cells, thereby coordinating a systemic anabolic response to nutrient availability [157]. It stimulates lipogenesis and lipid storage in adipose tissue [158]. Insulin therapy has been associated with an increased risk of HF, potentially mediated by EAT expansion and antinatriuretic effects [159,160,161,162]. Although data regarding EAT and insulin are limited, in a pilot study by Elisha et al., it has been shown that treatment with insulin analogs (detemir and glargine) among insulin-naïve uncontrolled patients with T2DM led to a reduction in EAT thickness, surprisingly. Furthermore, more pronounced EAT thickness reduction was observed with detemir [163].
6.2. Non-Diabetic Pharmacological Agents
- Statins. Growing evidence indicates that statins exert CV benefits beyond low-density lipoprotein (LDL) reduction, partly through modulation of EAT. High-intensity statin therapy has been associated with reductions in EAT volume and inflammatory activity, effects that appear to occur independently of lipid lowering. By attenuating the pro-inflammatory profile of EAT and perivascular adipose tissue, statins may contribute to decreased systemic inflammation and reduced progression of coronary atherosclerosis [164,165,166,167,168,169,170,171,172]. Experimental and clinical studies further suggest that these pleiotropic effects may improve myocardial structure and function. Statin therapy has been linked to attenuation of left ventricular diastolic dysfunction (LVDD), myocardial fibrosis, and microvascular impairment, particularly in obesity, dyslipidemia, and T2DM. Improvements in diastolic function have been observed with atorvastatin, pravastatin, simvastatin and rosuvastatin, while intensive statin regimens appear more effective than moderate-intensity therapy. Animal studies similarly demonstrate prevention or reversal of diastolic dysfunction following statin treatment [173,174,175,176,177,178,179,180,181,182,183]. In light of their pleiotropic action, observational clinical studies additionally suggest that statin use may reduce mortality risk in patients with HFpEF, whereas comparable benefits have not been consistently observed in HFrEF [184,185,186,187,188,189]. Recent meta-analytic evidence reinforces the concept that statins can significantly reduce EAT, although the magnitude of this effect appears modest. Current evidence indicates that the reduction in EAT achieved with statin therapy may be dose-dependent and partially attributable to anti-inflammatory mechanisms, including suppression of inflammatory cytokine secretion and modulation of peroxisome proliferator-activated receptor (PPAR) pathways. These findings support the emerging paradigm that atherosclerosis involves not only the vascular wall but also surrounding perivascular adipose tissues [190,191,192,193].
- 2.
- PCSK9i. Recent evidence demonstrating the expression of PCSK9 within EAT suggests that PCSK9 may constitute an important component of the EAT secretome. Moreover, EAT inflammation appears to be associated with increased local PCSK9 expression independently of circulating PCSK9 concentrations. These findings support the hypothesis that PCSK9 may contribute to the local inflammatory and metabolic activity of EAT, but further studies are required to determine whether targeted reduction in EAT inflammation or local PCSK9 expression may translate into improvements in EAT metabolism and reductions in CV risk [195]. In this context, PCSK9i, a novel class of lipid-lowering agents, have emerged as potential modulators of EAT expansion and dysfunction. Rivas-Gálvez et al. reported that treatment with the PCSK9 inhibitors evolocumab and alirocumab was associated with significant reductions in EAT volume after six months of therapy. These observations suggest that PCSK9 inhibition may exert pleiotropic cardiometabolic effects beyond low-density lipoprotein cholesterol reduction, potentially influencing adipose tissue remodeling and inflammatory pathways [196]. However, current evidence remains limited, particularly regarding the impact of PCSK9 inhibitors on cardiac diastolic function, warranting further investigation in larger prospective studies.
- 3.
- Trimetazidine (TMZ). Increased EAT thickness correlates with elevated concentrations of visfatin, an adipocytokine linked to obesity, insulin resistance, and CV disease. In addition to systemic secretion from adipocytes, visfatin is locally produced by EAT and cardiac cells, where it may exert autocrine and pro-fibrotic effects within the myocardium [197,198]. TMZ, a metabolic modulator used in ischemic heart disease and HF, has been shown to normalize circulating visfatin concentrations [199]. Considering the close association between EAT dysfunction and visfatin expression, TMZ may exert beneficial cardiometabolic effects partly through modulation of EAT-derived inflammatory signaling. These observations suggest a potential mechanistic link between trimetazidine therapy and EAT activity, warranting further investigation.
- 4.
- MRA, ACEi, ARB, ARNI. Renin–angiotensin–aldosterone system inhibitors, through their hormonal blockade, may play an important role in reducing EAT accumulation and its proinflammatory effects. Aldosterone is known to promote visceral and epicardial fat accumulation as well as adipose tissue inflammation, while activated renin-angiotensin system (RAS) and resultant production of angiotensin II is critically involved in obesity associated inflammation [200,201]. In an experimental mouse study using advanced magnetic resonance imaging techniques, eplerenone treatment reduced EAT volume and shifted its fatty acid composition toward greater unsaturation, which was associated with improved coronary microvascular function. Compared with untreated mice, eplerenone-treated animals showed lower saturated fatty acid fractions, reduced EAT mass, and improved myocardial perfusion reserve, suggesting beneficial effects on both adipose tissue metabolism and CV function [202]. Previous studies have shown that eplerenone can prevent and reverse obesity-related adipose inflammation and reduce CV death and HF hospitalization, especially in patients with abdominal obesity [203,204,205]. In the experimental study by Mitchell et al. was demonstrated that RAS inhibition reduces gene expression of inflammatory mediators in adipose tissue [206]. Furthermore, spironolactone and irbesartan appear to be more effective in patients with HFpEF and lower natriuretic peptide levels, possibly because these patients are more likely to have visceral adiposity and increased EAT [207,208]. These findings support the hypothesis that inhibition of aldosterone and RAS signaling may improve outcomes partly through modulation of visceral and epicardial adipose tissue activity.
- 5.
- Colchicine. Colchicine exerts anti-inflammatory effects primarily through irreversible binding to α/β-tubulin dimers, thereby inhibiting microtubule polymerization. In neutrophils, where colchicine preferentially accumulates due to reduced P-glycoprotein–mediated efflux, this results in impaired endothelial adhesion, migration, and transmigration out of vessels. Colchicine also suppresses several inflammatory mediators, including TNF-α, leukotriene B4, prostaglandin E2, thromboxane A2, and cyclooxygenase-2 activity. In addition, it inhibits neutrophil α-defensin release and neutrophil–platelet aggregation, potentially reducing thrombotic burden. Another key mechanism is inhibition of the NLRP3 inflammasome, leading to reduced production of IL-1β and IL-18 and attenuation of innate immune activation [216]. Clinical data suggest that colchicine may also modulate EAT-related inflammation. In patients undergoing AF ablation, lower left atrial EAT volume was associated with reduced early AF recurrence during short-term colchicine treatment, indicating a potential interaction between EAT burden and the anti-inflammatory efficacy of colchicine after ablation [217]. Similarly, in the EKSTROM trial, patients with stable CAD treated with colchicine demonstrated a significant reduction in EAT volume on serial cardiac CT over 12 months compared with placebo, although no significant change in EAT density was observed. These findings suggest that colchicine may favorably influence EAT volume and provide possible mechanistic insight into its CV protective effects [218].
7. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
References
- Iacobellis, G. Epicardial adipose tissue in contemporary cardiology. Nat. Rev. Cardiol. 2022, 19, 593–606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kershaw, E.E.; Flier, J.S. Adipose tissue as an endocrine organ. J. Clin. Endocrinol. Metab. 2004, 89, 2548–2556. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mazurek, T.; Zhang, L.; Zalewski, A.; Mannion, J.D.; Diehl, J.T.; Arafat, H.; Sarov-Blat, L.; O’Brien, S.; Keiper, E.A.; Johnson, A.G.; et al. Human epicardial adipose tissue is a source of inflammatory mediators. Circulation 2003, 108, 2460–2466. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- McAninch, E.A.; Fonseca, T.L.; Poggioli, R.; Panos, A.L.; Salerno, T.A.; Deng, Y.; Li, Y.; Bianco, A.C.; Iacobellis, G. Epicardial adipose tissue has a unique transcriptome modified in severe coronary artery disease. Obesity 2015, 23, 1267–1278. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iacobellis, G.; Willens, H.J. Echocardiographic epicardial fat: A review of research and clinical applications. J. Am. Soc. Echocardiogr. 2009, 22, 1311–1319. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gaborit, B.; Venteclef, N.; Ancel, P.; Pelloux, V.; Gariboldi, V.; Leprince, P.; Amour, J.; Hatem, S.N.; Jouve, E.; Dutour, A.; et al. Human epicardial adipose tissue has a specific transcriptomic signature depending on its anatomical peri-atrial, peri-ventricular, or peri-coronary location. Cardiovasc. Res. 2015, 108, 62–73. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhao, L.; Guo, Z.; Wang, P.; Zheng, M.; Yang, X.; Liu, Y.; Ma, Z.; Chen, M.; Yang, X. Proteomics of epicardial adipose tissue in patients with heart failure. J. Cell. Mol. Med. 2020, 24, 511–520. [Google Scholar] [PubMed]
- Camarena, V.; Sant, D.; Mohseni, M.; Salerno, T.; Zaleski, M.L.; Wang, G.; Iacobellis, G. Novel atherogenic pathways from the differential transcriptome analysis of diabetic epicardial adipose tissue. Nutr. Metab. Cardiovasc. Dis. 2017, 27, 739–750. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, L.; Zalewski, A.; Liu, Y.; Mazurek, T.; Cowan, S.; Martin, J.L.; Hofmann, S.M.; Vlassara, H.; Shi, Y. Diabetes-induced oxidative stress and low-grade inflammation in porcine coronary arteries. Circulation 2003, 108, 472–478. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wibmer, A.G.; Becher, T.; Eljalby, M.; Crane, A.; Andrieu, P.C.; Jiang, C.S.; Vaughan, R.; Schöder, H.; Cohen, P. Brown adipose tissue is associated with healthier body fat distribution and metabolic benefits independent of regional adiposity. Cell Rep. Med. 2021, 2, 100332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Vural, B.; Atalar, F.; Ciftci, C.; Demirkan, A.; Susleyici-Duman, B.; Gunay, D.; Akpinar, B.; Sagbas, E.; Ozbek, U.; Buyukdevrim, A.S. Presence of fatty-acid-binding protein 4 expression in human epicardial adipose tissue in metabolic syndrome. Cardiovasc. Pathol. 2008, 17, 392–398. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ridker, P.M.; Rifai, N.; Stampfer, M.J.; Hennekens, C.H. Plasma concentration of interleukin-6 and the risk of future myocardial infarction among apparently healthy men. Circulation 2000, 101, 1767–1772. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ridker, P.M.; Rifai, N.; Pfeffer, M.; Sacks, F.; Lepage, S.; Braunwald, E. Elevation of tumor necrosis factor-alpha and increased risk of recurrent coronary events after myocardial infarction. Circulation 2000, 101, 2149–2153. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lindahl, B.; Toss, H.; Siegbahn, A.; Venge, P.; Wallentin, L. Markers of myocardial damage and inflammation in relation to long-term mortality in unstable coronary artery disease. FRISC Study Group. Fragmin during Instability in Coronary Artery Disease. N. Engl. J. Med. 2000, 343, 1139–1147. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hotamisligil, G.S.; Arner, P.; Caro, J.F.; Atkinson, R.L.; Spiegelman, B.M. Increased adipose tissue expression of tumor necrosis factor-alpha in human obesity and insulin resistance. J. Clin. Investig. 1995, 95, 2409–2415. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kern, P.A.; Ranganathan, S.; Li, C.; Wood, L.; Ranganathan, G. Adipose tissue tumor necrosis factor and interleukin-6 expression in human obesity and insulin resistance. Am. J. Physiol. Endocrinol. Metab. 2001, 280, 745–751. [Google Scholar] [CrossRef] [Scilit]
- Hauck, A.K.; Bernlohr, D.A. Oxidative stress and lipotoxicity. J. Lipid Res. 2016, 57, 1976–1986. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ertunc, M.E.; Hotamisligil, G.S. Lipid signaling and lipotoxicity in metaflammation: Indications for metabolic disease pathogenesis and treatment. J. Lipid Res. 2016, 57, 2099–2114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chaurasia, B.; Summers, S.A. Ceramides—Lipotoxic Inducers of Metabolic Disorders. Trends Endocrinol. Metab. 2015, 26, 538–550, Erratum in Trends Endocrinol. Metab. 2018, 29, 66–67.. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Han, J.; Kaufman, R.J. The role of ER stress in lipid metabolism and lipotoxicity. J. Lipid Res. 2016, 57, 1329–1338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Montgomery, M.K.; De Nardo, W.; Watt, M.J. Impact of Lipotoxicity on Tissue “Cross Talk” and Metabolic Regulation. Physiology 2019, 34, 134–149. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Packer, M. Epicardial Adipose Tissue May Mediate Deleterious Effects of Obesity and Inflammation on the Myocardium. J. Am. Coll. Cardiol. 2018, 71, 2360–2372. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cinti, S.; Mitchell, G.; Barbatelli, G.; Murano, I.; Ceresi, E.; Faloia, E.; Wang, S.; Fortier, M.; Greenberg, A.S.; Obin, M.S. Adipocyte death defines macrophage localization and function in adipose tissue of obese mice and humans. J. Lipid Res. 2005, 46, 2347–2355. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Strissel, K.J.; Stancheva, Z.; Miyoshi, H.; Perfield, J.W., 2nd; DeFuria, J.; Jick, Z.; Greenberg, A.S.; Obin, M.S. Adipocyte death, adipose tissue remodeling, and obesity complications. Diabetes 2007, 56, 2910–2918. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sommer, G.; Kralisch, S.; Stangl, V.; Vietzke, A.; Köhler, U.; Stepan, H.; Faber, R.; Schubert, A.; Lössner, U.; Bluher, M.; et al. Secretory products from human adipocytes stimulate proinflammatory cytokine secretion from human endothelial cells. J. Cell. Biochem. 2009, 106, 729–737. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Johnston, E.K.; Abbott, R.D. Adipose Tissue Paracrine-, Autocrine-, and Matrix-Dependent Signaling during the Development and Progression of Obesity. Cells 2023, 12, 407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ludvik, B.; Nolan, J.J.; Baloga, J.; Sacks, D.; Olefsky, J. Effect of obesity on insulin resistance in normal subjects and patients with NIDDM. Diabetes 1995, 44, 1121–1125. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carey, V.J.; Walters, E.E.; Colditz, G.A.; Solomon, C.G.; Willett, W.C.; Rosner, B.A.; Speizer, F.E.; Manson, J.E. Body fat distribution and risk of non-insulin-dependent diabetes mellitus in women. The Nurses’ Health Study. Am. J. Epidemiol. 1997, 145, 614–619. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, L.; Chen, R.; Wang, H.; Liang, F. Mechanisms Linking Inflammation to Insulin Resistance. Int. J. Endocrinol. 2015, 2015, 508409. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hotamisligil, G.S.; Shargill, N.S.; Spiegelman, B.M. Adipose expression of tumor necrosis factor-alpha: Direct role in obesity-linked insulin resistance. Science 1993, 259, 87–91. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dandona, P.; Weinstock, R.; Thusu, K.; Abdel-Rahman, E.; Aljada, A.; Wadden, T. Tumor necrosis factor-alpha in sera of obese patients: Fall with weight loss. J. Clin. Endocrinol. Metab. 1998, 83, 2907–2910. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mohallem, R.; Aryal, U.K. Regulators of TNFα mediated insulin resistance elucidated by quantitative proteomics. Sci. Rep. 2020, 10, 20878. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hirokawa, J.; Sakaue, S.; Furuya, Y.; Ishii, J.; Hasegawa, A.; Tagami, S.; Kawakami, Y.; Sakai, M.; Nishi, S.; Nishihira, J. Tumor necrosis factor-alpha regulates the gene expression of macrophage migration inhibitory factor through tyrosine kinase-dependent pathway in 3T3-L1 adipocytes. J. Biochem. 1998, 123, 733–739. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Libby, P.; Ridker, P.M.; Maseri, A. Inflammation and atherosclerosis. Circulation 2002, 105, 1135–1143. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Azul, L.; Leandro, A.; Boroumand, P.; Klip, A.; Seiça, R.; Sena, C.M. Increased inflammation, oxidative stress and a reduction in antioxidant defense enzymes in perivascular adipose tissue contribute to vascular dysfunction in type 2 diabetes. Free Radic. Biol. Med. 2020, 146, 264–274. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cosson, E.; Nguyen, M.T.; Rezgani, I.; Berkane, N.; Pinto, S.; Bihan, H.; Tatulashvili, S.; Taher, M.; Sal, M.; Soussan, M.; et al. Epicardial adipose tissue volume and myocardial ischemia in asymptomatic people living with diabetes: A cross-sectional study. Cardiovasc. Diabetol. 2021, 20, 224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Parisi, V.; Rengo, G.; Perrone-Filardi, P.; Pagano, G.; Femminella, G.D.; Paolillo, S.; Petraglia, L.; Gambino, G.; Caruso, A.; Grimaldi, M.G.; et al. Increased Epicardial Adipose Tissue Volume Correlates with Cardiac Sympathetic Denervation in Patients with Heart Failure. Circ. Res. 2016, 118, 1244–1253. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- White, I.A. Cardiac Sympathetic Denervation in the Failing Heart: A Role for Epicardial Adipose Tissue. Circ. Res. 2016, 118, 1189–1191. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mazurek, T.; Opolski, G. Pericoronary adipose tissue: A novel therapeutic target in obesity-related coronary atherosclerosis. J. Am. Coll. Nutr. 2015, 34, 244–254. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hao, S.; Sui, X.; Wang, J.; Zhang, J.; Pei, Y.; Guo, L.; Liang, Z. Secretory products from epicardial adipose tissue induce adverse myocardial remodeling after myocardial infarction by promoting reactive oxygen species accumulation. Cell Death Dis. 2021, 12, 848. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Carena, M.C.; Badi, I.; Polkinghorne, M.; Akoumianakis, I.; Psarros, C.; Wahome, E.; Kotanidis, C.P.; Akawi, N.; Antonopoulos, A.S.; Chauhan, J.; et al. Role of Human Epicardial Adipose Tissue-Derived miR-92a-3p in Myocardial Redox State. J. Am. Coll. Cardiol. 2023, 82, 317–332. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Haemers, P.; Hamdi, H.; Guedj, K.; Suffee, N.; Farahmand, P.; Popovic, N.; Claus, P.; LePrince, P.; Nicoletti, A.; Jalife, J.; et al. Atrial fibrillation is associated with the fibrotic remodelling of adipose tissue in the subepicardium of human and sheep atria. Eur. Heart J. 2017, 38, 53–61. [Google Scholar] [PubMed]
- Nalliah, C.J.; Bell, J.R.; Raaijmakers, A.J.A.; Waddell, H.M.; Wells, S.P.; Bernasochi, G.B.; Montgomery, M.K.; Binny, S.; Watts, T.; Joshi, S.B.; et al. Epicardial Adipose Tissue Accumulation Confers Atrial Conduction Abnormality. J. Am. Coll. Cardiol. 2020, 76, 1197–1211. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Meulendijks, E.R.; Al-Shama, R.F.M.; Kawasaki, M.; Fabrizi, B.; Neefs, J.; Wesselink, R.; Ernault, A.C.; Piersma, S.; Pham, T.V.; Jimenez, C.R.; et al. Atrial epicardial adipose tissue abundantly secretes myeloperoxidase and activates atrial fibroblasts in patients with atrial fibrillation. J. Transl. Med. 2023, 21, 366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oba, K.; Maeda, M.; Maimaituxun, G.; Yamaguchi, S.; Arasaki, O.; Fukuda, D.; Yagi, S.; Hirata, Y.; Nishio, S.; Iwase, T.; et al. Effect of the Epicardial Adipose Tissue Volume on the Prevalence of Paroxysmal and Persistent Atrial Fibrillation. Circ. J. 2018, 82, 1778–1787. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schram-Serban, C.; Heida, A.; Roos-Serote, M.C.; Knops, P.; Kik, C.; Brundel, B.; Bogers, A.J.J.C.; de Groot, N.M.S. Heterogeneity in Conduction Underlies Obesity-Related Atrial Fibrillation Vulnerability. Circ. Arrhythmia Electrophysiol. 2020, 13, e008161. [Google Scholar] [CrossRef] [Scilit]
- Bekar, L.; Kalçık, M.; Çelik, O.; Alp, Ç.; Yetim, M.; Doğan, T.; Ekinözü, İ.; Karaarslan, O.; Çamkıran, V.; Karavelioğlu, Y.; et al. Presence of fragmented QRS is associated with increased epicardial adipose tissue thickness in hypertensive patients. J. Clin. Ultrasound 2019, 47, 345–350. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shen, J.; Zhu, D.; Chen, L.; Cang, J.; Zhao, Z.; Ji, Y.; Liu, S.; Miao, H.; Liu, Y.; Zhou, Q.; et al. Relationship between epicardial adipose tissue measured by computed tomography and premature ventricular complexes originating from different sites. Europace 2023, 25, 102, Erratum in Europace 2023, 25, 138.. [Google Scholar] [CrossRef] [Scilit]
- Ernault, A.C.; Meijborg, V.M.F.; Coronel, R. Modulation of Cardiac Arrhythmogenesis by Epicardial Adipose Tissue: JACC State-of-the-Art Review. J. Am. Coll. Cardiol. 2021, 78, 1730–1745. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kankaanpää, M.; Lehto, H.R.; Pärkkä, J.P.; Komu, M.; Viljanen, A.; Ferrannini, E.; Knuuti, J.; Nuutila, P.; Parkkola, R.; Iozzo, P. Myocardial triglyceride content and epicardial fat mass in human obesity: Relationship to left ventricular function and serum free fatty acid levels. J. Clin. Endocrinol. Metab. 2006, 91, 4689–4695. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sepehri Shamloo, A.; Schoene, K.; Stauber, A.; Darma, A.; Dagres, N.; Dinov, B.; Bertagnolli, L.; Hilbert, S.; Müssigbrodt, A.; Husser, D.; et al. Epicardial adipose tissue thickness as an independent predictor of ventricular tachycardia recurrence following ablation. Heart Rhythm 2019, 16, 1492–1498. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grubić Rotkvić, P.; Planinić, Z.; Liberati Pršo, A.M.; Šikić, J.; Galić, E.; Rotkvić, L. The Mystery of Diabetic Cardiomyopathy: From Early Concepts and Underlying Mechanisms to Novel Therapeutic Possibilities. Int. J. Mol. Sci. 2021, 22, 5973. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Seferović, P.M.; Paulus, W.J.; Rosano, G.; Polovina, M.; Petrie, M.C.; Jhund, P.S.; Tschöpe, C.; Sattar, N.; Piepoli, M.; Papp, Z.; et al. Diabetic myocardial disorder. A clinical consensus statement of the Heart Failure Association of the ESC and the ESC Working Group on Myocardial & Pericardial Diseases. Eur. J. Heart Fail. 2024, 26, 1893–1903. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Pop-Busui, R.; Januzzi, J.L.; Bruemmer, D.; Butalia, S.; Green, J.B.; Horton, W.B.; Knight, C.; Levi, M.; Rasouli, N.; Richardson, C.R. Heart Failure: An Underappreciated Complication of Diabetes. A Consensus Report of the American Diabetes Association. Diabetes Care 2022, 45, 1670–1690. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kenny, H.C.; Abel, E.D. Heart Failure in Type 2 Diabetes Mellitus. Circ. Res. 2019, 124, 121–141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bugger, H.; Abel, E.D. Molecular mechanisms of diabetic cardiomyopathy. Diabetologia 2014, 57, 660–671. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jørgensen, P.G.; Jensen, M.T.; Biering-Sørensen, T.; Mogelvang, R.; Fritz-Hansen, T.; Vilsbøll, T.; Rossing, P.; Jensen, J.S. Burden of Uncontrolled Metabolic Risk Factors and Left Ventricular Structure and Function in Patients with Type 2 Diabetes Mellitus. J. Am. Heart Assoc. 2018, 7, e008856. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, Y.; Liu, B.; Li, Y.; Jing, X.; Deng, S.; Yan, Y.; She, Q. Epicardial fat tissue in patients with diabetes mellitus: A systematic review and meta-analysis. Cardiovasc. Diabetol. 2019, 18, 3. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Đuzel Čokljat, A.; Grubić Rotkvić, P.; Čokljat, D.; Ferri Certić, J.; Babić, Z. Epicardial adipose tissue in diabetic myocardial disorder: Role of echocardiography. World J. Diabetes 2025, 16, 107640. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- van Woerden, G.; van Veldhuisen, D.J.; Westenbrink, B.D.; de Boer, R.A.; Rienstra, M.; Gorter, T.M. Connecting epicardial adipose tissue and heart failure with preserved ejection fraction: Mechanisms, management and modern perspectives. Eur. J. Heart Fail. 2022, 24, 2238–2250. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gorter, T.M.; van Woerden, G.; Rienstra, M.; Dickinson, M.G.; Hummel, Y.M.; Voors, A.A.; Hoendermis, E.S.; van Veldhuisen, D.J. Epicardial Adipose Tissue and Invasive Hemodynamics in Heart Failure with Preserved Ejection Fraction. JACC Heart Fail. 2020, 8, 667–676. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Koepp, K.E.; Obokata, M.; Reddy, Y.N.V.; Olson, T.P.; Borlaug, B.A. Hemodynamic and Functional Impact of Epicardial Adipose Tissue in Heart Failure with Preserved Ejection Fraction. JACC Heart Fail. 2020, 8, 657–666. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Oduah, M.T.; Sundaram, V.; Reddy, Y.N. Epicardial Fat in Heart Failure with Preserved Ejection Fraction: Bad Actor or Just Lying Around? Card. Fail. Rev. 2023, 9, e06. [Google Scholar] [CrossRef] [Scilit]
- Obokata, M.; Reddy, Y.N.V.; Pislaru, S.V.; Melenovsky, V.; Borlaug, B.A. Evidence Supporting the Existence of a Distinct Obese Phenotype of Heart Failure with Preserved Ejection Fraction. Circulation 2017, 136, 6–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ng, A.C.; Delgado, V.; Bertini, M.; van der Meer, R.W.; Rijzewijk, L.J.; Shanks, M.; Nucifora, G.; Smit, J.W.; Diamant, M.; Romijn, J.A.; et al. Findings from left ventricular strain and strain rate imaging in asymptomatic patients with type 2 diabetes mellitus. Am. J. Cardiol. 2009, 104, 1398–1401. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choy, M.; Huang, Y.; Peng, Y.; Liang, W.; He, X.; Chen, C.; Li, J.; Zhu, W.; Wei, F.F.; Dong, Y.; et al. Association between epicardial adipose tissue and incident heart failure mediating by alteration of natriuretic peptide and myocardial strain. BMC Med. 2023, 21, 117. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, N.; Cao, Y.; Li, Y.; Zhang, K.; Zhang, L.; Luo, Q.; Sun, W.; Shi, H. Predictive value of epicardial adipose tissue volume for early detection of left ventricular dysfunction in patients suspected of coronary artery disease. Clin. Radiol. 2025, 81, 106760. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Schulz, A.; Backhaus, S.J.; Lange, T.; Evertz, R.; Kutty, S.; Kowallick, J.T.; Hasenfuß, G.; Schuster, A. Impact of epicardial adipose tissue on cardiac function and morphology in patients with diastolic dysfunction. ESC Heart Fail. 2024, 11, 2013–2022. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, M.C.; Liu, H.K.; Tsai, C.C.; Su, Y.T.; Wu, J.R. Epicardial Adipose Tissue Was Highly Associated with Reduction in Left Ventricular Diastolic Function as Early as in Adolescence. Acta Cardiol. Sin. 2022, 38, 601–611. [Google Scholar] [PubMed]
- Topuz, M.; Dogan, A. The effect of epicardial adipose tissue thickness on left ventricular diastolic functions in patients with normal coronary arteries. Kardiol. Pol. 2017, 75, 196–203. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- de Wit-Verheggen, V.H.W.; Altintas, S.; Spee, R.J.M.; Mihl, C.; van Kuijk, S.M.J.; Wildberger, J.E.; Schrauwen-Hinderling, V.B.; Kietselaer, B.L.J.H.; van de Weijer, T. Pericardial fat and its influence on cardiac diastolic function. Cardiovasc. Diabetol. 2020, 19, 129, Erratum in Cardiovasc. Diabetol. 2024, 23, 271.. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Setti, M.; Benfari, G.; Mele, D.; Rossi, A.; Ballo, P.; Galderisi, M.; Henein, M.; Nistri, S. Discrepancies in Assessing Diastolic Function in Pre-Clinical Heart Failure Using Different Algorithms-A Primary Care Study. Diagnostics 2020, 10, 850. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ishikawa, H.; Sugiyama, T.; Otsuka, K.; Yamaura, H.; Hojo, K.; Kono, Y.; Ito, A.; Yamazaki, T.; Shimada, K.; Kasayuki, N.; et al. Impact of epicardial adipose tissue on diastolic dysfunction in patients with chronic coronary syndrome and preserved left ventricular ejection fraction. Eur. Heart J.-Imaging Methods Pract. 2024, 2, qyae056. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mancio, J.; Azevedo, D.; Fragao-Marques, M.; Falcao-Pires, I.; Leite-Moreira, A.; Lunet, N.; Fontes-Carvalho, R.; Bettencourt, N. Meta-Analysis of Relation of Epicardial Adipose Tissue Volume to Left Atrial Dilation and to Left Ventricular Hypertrophy and Functions. Am. J. Cardiol. 2019, 123, 523–531. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Christensen, R.H.; Hansen, C.S.; von Scholten, B.J.; Jensen, M.T.; Pedersen, B.K.; Schnohr, P.; Vilsbøll, T.; Rossing, P.; Jørgensen, P.G. Epicardial and pericardial adipose tissues are associated with reduced diastolic and systolic function in type 2 diabetes. Diabetes Obes. Metab. 2019, 21, 2006–2011. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nakazato, R.; Rajani, R.; Cheng, V.Y.; Shmilovich, H.; Nakanishi, R.; Otaki, Y.; Gransar, H.; Slomka, P.J.; Hayes, S.W.; Thomson, L.E.; et al. Weight change modulates epicardial fat burden: A 4-year serial study with non-contrast computed tomography. Atherosclerosis 2012, 220, 139–144. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Willens, H.J.; Byers, P.; Chirinos, J.A.; Labrador, E.; Hare, J.M.; de Marchena, E. Effects of weight loss after bariatric surgery on epicardial fat measured using echocardiography. Am. J. Cardiol. 2007, 99, 1242–1245. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Graziani, F.; Leone, A.M.; Cialdella, P.; Basile, E.; Pennestri, F.; Della Bona, R.; Iaconelli, A.; Liuzzo, G.; Biasucci, L.M.; Cardillo, M.T.; et al. Effects of bariatric surgery on cardiac remodeling: Clinical and pathophysiologic implications. Int. J. Cardiol. 2013, 168, 4277–4279. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Henry, J.A.; Abdesselam, I.; Deal, O.; Lewis, A.J.; Rayner, J.; Bernard, M.; Dutour, A.; Gaborit, B.; Kober, F.; Soghomonian, A.; et al. Changes in epicardial and visceral adipose tissue depots following bariatric surgery and their effect on cardiac geometry. Front. Endocrinol. 2023, 14, 1092777. [Google Scholar] [CrossRef] [Scilit]
- Asteria, C.; Secchi, F.; Morricone, L.; Malavazos, A.E.; Francesconi, S.; Milani, V.; Giovanelli, A. Open-bore MRI Scanner Assessment of Epicardial Adipose Tissue after Bariatric Surgery: A Pilot Study. Endocr. Metab. Immune Disord. Drug Targets 2025, 25, 173–188. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hunt, S.C.; Davidson, L.E.; Adams, T.D.; Ranson, L.; McKinlay, R.D.; Simper, S.C.; Litwin, S.E. Associations of Visceral, Subcutaneous, Epicardial, and Liver Fat with Metabolic Disorders up to 14 Years After Weight Loss Surgery. Metab. Syndr. Relat. Disord. 2021, 19, 83–92. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mikamo, H.; Jiang, M.; Noro, M.; Suzuki, Y.; Hiruta, N.; Unoki-Kubota, H.; Schneider, W.J.; Bujo, H. Susceptibilities of epicardial and subcutaneous fat tissue for browning-gene expression and diet-induced volume reduction are different. Mol. Med. Rep. 2018, 17, 6542–6550. [Google Scholar] [PubMed]
- Kuleta, K.; Krauz, K.; Żmuda, J.; Momot, K.; Zarębiński, M.; Poprawa, I.; Wojciechowska, M. Pharmacological and Non-Pharmacological Interventions in Diabetes Mellitus: Effects on Epicardial Adipose Tissue. Int. J. Mol. Sci. 2025, 26, 9271. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Visseren, F.L.J.; Mach, F.; Smulders, Y.M.; Carballo, D.; Koskinas, K.C.; Bäck, M.; Benetos, A.; Biffi, A.; Boavida, J.-M.; Capodanno, D.; et al. 2021 ESC guidelines on cardiovascular disease prevention in clinical practice. Eur. Heart J. 2021, 42, 3227–3337. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Barrio-Lopez, M.T.; Ruiz-Canela, M.; Goni, L.; Valiente, A.M.; Garcia, S.R.; de la O, V.; Anton, B.D.; Fernandez-Friera, L.; Castellanos, E.; Martínez-González, M.A.; et al. Mediterranean diet and epicardial adipose tissue in patients with atrial fibrillation treated with ablation: A substudy of the ‘PREDIMAR’ trial. Eur. J. Prev. Cardiol. 2024, 31, 348–355. [Google Scholar] [PubMed]
- Derosa, G.; D’Angelo, A.; Angelini, F.; Belli, L.; Cicero, A.F.G.; Da Ros, R.; De Pergola, G.; Gaudio, G.V.; Lupi, A.; Sartore, G.; et al. Nutraceuticals and Supplements in Management of Prediabetes and Diabetes. Nutrients 2024, 17, 14. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Huang, Q.; Zhan, J.; Gui, Y.; Ma, M.; Li, E. Effects of different vitamin D supplements on body fat distribution and glucolipid metabolism in patients with obesity-associated metabolic syndrome: A meta-analysis. Medicine 2026, 105, e47436. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Christensen, R.H.; Wedell-Neergaard, A.S.; Lehrskov, L.L.; Legaard, G.E.; Dorph, E.; Larsen, M.K.; Launbo, N.; Fagerlind, S.R.; Seide, S.K.; Nymand, S.; et al. Effect of Aerobic and Resistance Exercise on Cardiac Adipose Tissues: Secondary Analyses from a Randomized Clinical Trial. JAMA Cardiol. 2019, 4, 778–787. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wilund, K.R.; Tomayko, E.J.; Wu, P.T.; Ryong Chung, H.; Vallurupalli, S.; Lakshminarayanan, B.; Fernhall, B. Intradialytic exercise training reduces oxidative stress and epicardial fat: A pilot study. Nephrol. Dial. Transplant. 2010, 25, 2695–2701. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rosety, M.A.; Pery, M.T.; Rodriguez-Pareja, M.A.; Diaz, A.; Rosety, J.; Garcia, N.; Brenes-Martin, F.; Rosety-Rodriguez, M.; Toro, R.; Ordonez, F.J.; et al. A Short-Term Circuit Resistance Programme Reduced Epicardial Fat in Obese Aged Women. Nutr. Hosp. 2015, 32, 2193–2197. [Google Scholar] [PubMed]
- Kim, M.K.; Tomita, T.; Kim, M.J.; Sasai, H.; Maeda, S.; Tanaka, K. Aerobic exercise training reduces epicardial fat in obese men. J. Appl. Physiol. 2009, 106, 5–11. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhou, J.; Gao, X.; Zhang, D.; Jiang, C.; Yu, W. Effects of breaking up prolonged sitting via exercise snacks intervention on the body composition and plasma metabolomics of sedentary obese adults: A randomized controlled trial. Endocr. J. 2025, 72, 183–192. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Honkala, S.M.; Motiani, K.K.; Eskelinen, J.J.; Savolainen, A.; Saunavaara, V.; Virtanen, K.A.; Loyttyniemi, E.; Kapanen, J.; Knuuti, J.; Kalliokoski, K.K.; et al. Exercise Training Reduces Intrathoracic Fat Regardless of Defective Glucose Tolerance. Med. Sci. Sports Exerc. 2017, 49, 1313–1322. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Milanese, G.; Silva, M.; Bruno, L.; Goldoni, M.; Benedetti, G.; Rossi, E.; Ferrari, C.; Grutta, L.; Maffei, E.; Toia, P.; et al. Quantification of epicardial fat with cardiac CT angiography and association with cardiovascular risk factors in symptomatic patients: From the ALTER-BIO registry. Diagn. Interv. Radiol. 2019, 25, 35–41. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Monti, M.; Monti, A.; Murdolo, G.; Di Renzi, P.; Pirro, M.R.; Borgognoni, F.; Vincentelli, G.M. Correlation between epicardial fat and cigarette smoking: CT imaging in patients with metabolic syndrome. Scand. Cardiovasc. J. 2014, 48, 317–322. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gac, P.; Czerwinska, K.; Poreba, M.; Macek, P.; Mazur, G.; Poreba, R. Environmental Tobacco Smoke Exposure Estimated Using the SHSES Scale and Epicardial Adipose Tissue Thickness in Hypertensive Patients. Cardiovasc. Toxicol. 2021, 21, 79–87. [Google Scholar] [PubMed]
- Messineo, L.; Bakker, J.P.; Cronin, J.; Yee, J.; White, D.P. Obstructive sleep apnea and obesity: A review of epidemiology, pathophysiology and the effect of weight-loss treatments. Sleep Med. Rev. 2024, 78, 101996. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Young, T.; Peppard, P.E.; Gottlieb, D.J. Epidemiology of obstructive sleep apnea. Am. J. Respir. Crit. Care Med. 2002, 165, 1217–1239. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Varghese, R.T.; Akurati, S.; Iacobellis, G. Epicardial fat and sleep apnea: Perspective mechanisms, diagnostics, and therapeutics. Obes. Endocrinol. 2025, 1, wjaf009. [Google Scholar] [CrossRef] [Scilit]
- Parekh, A. Hypoxic burden: Definitions, pathophysiological concepts, methods of evaluation, and clinical relevance. Curr. Opin. Pulm. Med. 2024, 30, 600–606. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beaudin, A.E.; Hanly, P.J.; Raneri, J.K.; Younes, M.; Pun, M.; Anderson, T.J.; Poulin, M.J. Impact of intermittent hypoxia on human vascular responses during sleep. Exp. Neurol. 2022, 347, 113897. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Adeva-Andany, M.M.; Domínguez-Montero, A.; Castro-Quintela, E.; Funcasta-Calderón, R.; Fernández-Fernández, C. Hypoxia-Induced Insulin Resistance Mediates the Elevated Cardiovascular Risk in Patients with Obstructive Sleep Apnea: A Comprehensive Review. Rev. Cardiovasc. Med. 2024, 25, 231. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kostopoulos, K.; Alhanatis, E.; Pampoukas, K.; Georgiopoulos, G.; Zourla, A.; Panoutsopoulos, A.; Kallianos, A.; Velentza, L.; Zarogoulidis, P.; Trakada, G. CPAP therapy induces favorable short-term changes in epicardial fat thickness and vascular and metabolic markers in OSAHS. Sleep. Breath. 2016, 20, 483–493. [Google Scholar] [PubMed]
- Palanisamy, S.; Yien, E.L.H.; Shi, L.W.; Si, L.Y.; Qi, S.H.; Ling, L.S.C.; Lun, T.W.; Chen, Y.N. Systematic Review of Efficacy and Safety of Newer Antidiabetic Drugs Approved from 2013 to 2017 in Controlling HbA1c in Diabetes Patients. Pharmacy 2018, 6, 57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wang, C.P.; Hsu, H.L.; Hung, W.C.; Yu, T.H.; Chen, Y.H.; Chiu, C.A.; Lu, L.F.; Chung, F.M.; Shin, S.J.; Lee, Y.J. Increased epicardial adipose tissue (EAT) volume in type 2 diabetes mellitus and association with metabolic syndrome and severity of coronary atherosclerosis. Clin. Endocrinol. 2009, 70, 876–882. [Google Scholar] [CrossRef] [Scilit]
- Philouze, C.; Obert, P.; Nottin, S.; Benamor, A.; Barthez, O.; Aboukhoudir, F. Dobutamine Stress Echocardiography Unmasks Early Left Ventricular Dysfunction in Asymptomatic Patients with Uncomplicated Type 2 Diabetes: A Comprehensive Two-Dimensional Speckle-Tracking Imaging Study. J. Am. Soc. Echocardiogr. 2018, 31, 587–597. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Altara, R.; Giordano, M.; Nordén, E.S.; Cataliotti, A.; Kurdi, M.; Bajestani, S.N.; Booz, G.W. Targeting Obesity and Diabetes to Treat Heart Failure with Preserved Ejection Fraction. Front. Endocrinol. 2017, 8, 160. [Google Scholar] [CrossRef] [Scilit]
- Udell, J.A.; Cavender, M.A.; Bhatt, D.L.; Chatterjee, S.; Farkouh, M.E.; Scirica, B.M. Glucose lowering drugs or strategies and cardiovascular outcomes in patients with or at risk for type 2 diabetes: A meta-analysis of randomized controlled trials. Lancet Diabetes Endocrinol. 2015, 3, 356–366. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cignarelli, A.; Giorgino, F.; Vettor, R. Pharmacologic agents for type 2 diabetes therapy and regulation of adipogenesis. Arch. Physiol. Biochem. 2013, 119, 139–150. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bailey, C.J.; Turner, R.C. Metformin. N. Engl. J. Med. 1996, 334, 574–579. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Emslie-Smith, A.M.; Boyle, D.I.; Evans, J.M.; Sullivan, F.; Morris, A.D.; DARTS/MEMO Collaboration. Contraindications to metformin therapy in patients with Type 2 diabetes—A population-based study of adherence to prescribing guidelines. Diabet. Med. 2001, 18, 483–488. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ziyrek, M.; Kahraman, S.; Ozdemir, E.; Dogan, A. Metformin monotherapy significantly decreases epicardial adipose tissue thickness in newly diagnosed type 2 diabetes patients. Rev. Port. Cardiol. 2019, 38, 419–423. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Gunes, H.; Gunes, H.; Ozmen, S.; Celik, E.; Temiz, F. Effects of metformin on epicardial adipose tissue and atrial electromechanical delay of obese children with insulin resistance. Cardiol. Young 2020, 30, 1429–1432. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, B.; Po, S.S.; Zhang, B.; Bai, F.; Li, J.; Qin, F.; Liu, N.; Sun, C.; Xiao, Y.; Tu, T.; et al. Metformin regulates adiponectin signalling in epicardial adipose tissue and reduces atrial fibrillation vulnerability. J. Cell. Mol. Med. 2020, 24, 7751–7766. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Elia, E.M.; Pustovrh, C.; Amalfi, S.; Devoto, L.; Motta, A.B. Link between metformin and the peroxisome proliferator-activated receptor gamma pathway in the uterine tissue of hyperandrogenized prepubertal mice. Fertil. Steril. 2011, 95, 2534–2537.e1. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sun, L.; Xu, Y.W.; Han, J.; Liang, H.; Wang, N.; Cheng, Y. 12/15-Lipoxygenase metabolites of arachidonic acid activate PPARγ: A possible neuroprotective effect in ischemic brain. J. Lipid Res. 2015, 56, 502–514. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mansour, H.H.; El Kiki, S.M.; Galal, S.M. Metformin and low dose radiation modulates cisplatin-induced oxidative injury in rat via PPAR-gamma and MAPK pathways. Arch. Biochem. Biophys. 2017, 616, 13–19. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Su, J.R.; Lu, Z.H.; Su, Y.; Zhao, N.; Dong, C.L.; Sun, L.; Zhao, S.F.; Li, Y. Relationship of Serum Adiponectin Levels and Metformin Therapy in Patients with Type 2 Diabetes. Horm. Metab. Res. 2016, 48, 92–98. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Evia-Viscarra, M.L.; Rodea-Montero, E.R.; Apolinar-Jimenez, E.; Munoz-Noriega, N.; Garcia-Morales, L.M.; Leanos-Perez, C.; Figueroa-Barron, M.; Sanchez-Fierros, D.; Reyes-Garcia, J.G. The effects of metformin on inflammatory mediators in obese adolescents with insulin resistance: Controlled randomized clinical trial. J. Pediatr. Endocrinol. Metab. 2012, 25, 41–49. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iacobellis, G.; Mohseni, M.; Bianco, S.D.; Banga, P.K. Liraglutide causes large and rapid epicardial fat reduction. Obesity 2017, 25, 311–316. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dormandy, J.A.; Charbonnel, B.; Eckland, D.J.; Erdmann, E.; Massi-Benedetti, M.; Moules, I.K.; Skene, A.M.; Tan, M.H.; Lefèbvre, P.J.; Murray, G.D.; et al. PROactive Investigators. Secondary prevention of macrovascular events in patients with type 2 diabetes in the PROactive Study (PROspective pioglitAzone Clinical Trial In macroVascular Events): A randomised controlled trial. Lancet 2005, 366, 1279–1289. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Filipova, E.; Uzunova, K.; Kalinov, K.; Vekov, T. Effects of pioglitazone therapy on blood parameters, weight and BMI: A meta-analysis. Diabetol. Metab. Syndr. 2017, 9, 90. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhang, F.; Pan, X.; Zhang, X.; Tong, N. The effect of thiazolidinediones on body fat redistribution in adults: A systematic review and meta-analysis of randomized controlled trials. Obes. Rev. 2024, 25, e13675. [Google Scholar] [PubMed]
- Moody, A.J.; Molina-Wilkins, M.; Clarke, G.D.; Merovci, A.; Solis-Herrera, C.; Cersosimo, E.; Chilton, R.J.; Iozzo, P.; Gastaldelli, A.; Abdul-Ghani, M.; et al. Pioglitazone reduces epicardial fat and improves diastolic function in patients with type 2 diabetes. Diabetes Obes. Metab. 2023, 25, 426–434. [Google Scholar] [PubMed]
- Jonker, J.T.; Lamb, H.J.; van der Meer, R.W.; Rijzewijk, L.J.; Menting, L.J.; Diamant, M.; Bax, J.J.; de Roos, A.; Romijn, J.A.; Smit, J.W. Pioglitazone compared with metformin increases pericardial fat volume in patients with type 2 diabetes mellitus. J. Clin. Endocrinol. Metab. 2010, 95, 456–460. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Sacks, H.S.; Fain, J.N.; Cheema, P.; Bahouth, S.W.; Garrett, E.; Wolf, R.Y.; Wolford, D.; Samaha, J. Inflammatory genes in epicardial fat contiguous with coronary atherosclerosis in the metabolic syndrome and type 2 diabetes: Changes associated with pioglitazone. Diabetes Care 2011, 34, 730–733. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Distel, E.; Penot, G.; Cadoudal, T.; Balguy, I.; Durant, S.; Benelli, C. Early induction of a brown-like phenotype by rosiglitazone in the epicardial adipose tissue of fatty Zucker rats. Biochimie 2012, 94, 1660–1667. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Zhu, J.; Yu, X.; Zheng, Y.; Li, J.; Wang, Y.; Lin, Y.; He, Z.; Zhao, W.; Chen, C.; Qiu, K.; et al. Association of glucose-lowering medications with cardiovascular outcomes: An umbrella review and evidence map. Lancet Diabetes Endocrinol. 2020, 8, 192–205. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Karagiannis, T.; Paschos, P.; Paletas, K.; Matthews, D.R.; Tsapas, A. Dipeptidyl peptidase-4 inhibitors for treatment of type 2 diabetes mellitus in the clinical setting: Systematic review and meta-analysis. BMJ 2012, 344, e1369. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- ElSayed, N.A.; Aleppo, G.; Aroda, V.R.; Bannuru, R.R.; Brown, F.M.; Bruemmer, D.; Collins, B.S.; Das, S.R.; Hilliard, M.E.; Isaacs, D.; et al. 10. Cardiovascular Disease and Risk Management: Standards of Care in Diabetes-2023. Diabetes Care 2023, 46, S158–S190. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lima-Martinez, M.M.; Paoli, M.; Rodney, M.; Balladares, N.; Contreras, M.; D’Marco, L.; Iacobellis, G. Effect of sitagliptin on epicardial fat thickness in subjects with type 2 diabetes and obesity: A pilot study. Endocrine 2016, 51, 448–455. [Google Scholar] [PubMed]
- Hiruma, S.; Shigiyama, F.; Hisatake, S.; Mizumura, S.; Shiraga, N.; Hori, M.; Ikeda, T.; Hirose, T.; Kumashiro, N. A prospective randomized study comparing effects of empagliflozin to sitagliptin on cardiac fat accumulation, cardiac function, and cardiac metabolism in patients with early-stage type 2 diabetes: The ASSET study. Cardiovasc. Diabetol. 2021, 20, 32. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hirose, M.; Takano, H.; Hasegawa, H.; Tadokoro, H.; Hashimoto, N.; Takemura, G.; Kobayashi, Y. The effects of dipeptidyl peptidase-4 on cardiac fibrosis in pressure overload-induced heart failure. J. Pharmacol. Sci. 2017, 135, 164–173. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mulvihill, E.E.; Varin, E.M.; Ussher, J.R.; Campbell, J.E.; Bang, K.W.; Abdullah, T.; Baggio, L.L.; Drucker, D.J. Inhibition of Dipeptidyl Peptidase-4 Impairs Ventricular Function and Promotes Cardiac Fibrosis in High Fat-Fed Diabetic Mice. Diabetes 2016, 65, 742–754. [Google Scholar] [PubMed]
- Palmer, S.C.; Tendal, B.; Mustafa, R.A.; Vandvik, P.O.; Li, S.; Hao, Q.; Tunnicliffe, D.; Ruospo, M.; Natale, P.; Saglimbene, V.; et al. Sodium-glucose cotransporter protein-2 (SGLT-2) inhibitors and glucagon-like peptide-1 (GLP-1) receptor agonists for type 2 diabetes: Systematic review and network meta-analysis of randomised controlled trials. BMJ 2021, 372, m4573. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Malavazos, A.E.; Iacobellis, G.; Dozio, E.; Basilico, S.; Di Vincenzo, A.; Dubini, C.; Menicanti, L.; Vianello, E.; Meregalli, C.; Ruocco, C.; et al. Human epicardial adipose tissue expresses glucose-dependent insulinotropic polypeptide, glucagon, and glucagon-like peptide-1 receptors as potential targets of pleiotropic therapies. Eur. J. Prev. Cardiol. 2023, 30, 680–693. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iacobellis, G.; Camarena, V.; Sant, D.W.; Wang, G. Human Epicardial Fat Expresses Glucagon-Like Peptide 1 and 2 Receptors Genes. Horm. Metab. Res. 2017, 49, 625–630. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Morano, S.; Romagnoli, E.; Filardi, T.; Nieddu, L.; Mandosi, E.; Fallarino, M.; Turinese, I.; Dagostino, M.P.; Lenzi, A.; Carnevale, V. Short-term effects of glucagon-like peptide 1 (GLP-1) receptor agonists on fat distribution in patients with type 2 diabetes mellitus: An ultrasonography study. Acta Diabetol. 2015, 52, 727–732. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Iacobellis, G.; Villasante Fricke, A.C. Effects of Semaglutide Versus Dulaglutide on Epicardial Fat Thickness in Subjects with Type 2 Diabetes and Obesity. J. Endocr. Soc. 2020, 4, bvz042. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Myasoedova, V.A.; Parisi, V.; Moschetta, D.; Valerio, V.; Conte, M.; Massaiu, I.; Bozzi, M.; Celeste, F.; Leosco, D.; Iaccarino, G.; et al. Efficacy of cardiometabolic drugs in reduction of epicardial adipose tissue: A systematic review and meta-analysis. Cardiovasc. Diabetol. 2023, 22, 23. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dozio, E.; Vianello, E.; Malavazos, A.E.; Tacchini, L.; Schmitz, G.; Iacobellis, G.; Corsi Romanelli, M.M. Epicardial adipose tissue GLP-1 receptor is associated with genes involved in fatty acid oxidation and white-to-brown fat differentiation: A target to modulate cardiovascular risk? Int. J. Cardiol. 2019, 292, 218–224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hong, J.Y.; Park, K.Y.; Kim, B.J.; Hwang, W.M.; Kim, D.H.; Lim, D.M. Effects of Short-Term Exenatide Treatment on Regional Fat Distribution, Glycated Hemoglobin Levels, and Aortic Pulse Wave Velocity of Obese Type 2 Diabetes Mellitus Patients. Endocrinol. Metab. 2016, 31, 80–85. [Google Scholar] [CrossRef] [Scilit]
- Vlachopoulos, C.; Aznaouridis, K.; Stefanadis, C. Prediction of cardiovascular events and all-cause mortality with arterial stiffness: Asystematic review and meta-analysis. J. Am. Coll. Cardiol. 2010, 55, 1318–1327. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nguyen, T.D.; Shingu, Y.; Amorim, P.A.; Schenkl, C.; Schwarzer, M.; Doenst, T. GLP-1 Improves Diastolic Function and Survival in Heart Failure with Preserved Ejection Fraction. J. Cardiovasc. Transl. Res. 2018, 11, 259–267. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hummel, C.S.; Lu, C.; Loo, D.D.; Hirayama, B.A.; Voss, A.A.; Wright, E.M. Glucose transport by human renal Na+/D-glucose cotransporters SGLT1 and SGLT2. Am. J. Physiol. Cell Physiol. 2011, 300, C14–C21. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Grubić Rotkvić, P.; Cigrovski Berković, M.; Bulj, N.; Rotkvić, L.; Ćelap, I. Sodium-glucose cotransporter 2 inhibitors’ mechanisms of action in heart failure. World J. Diabetes 2020, 11, 269–279. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cinti, F.; Leccisotti, L.; Sorice, G.P.; Capece, U.; D’Amario, D.; Lorusso, M.; Gugliandolo, S.; Morciano, C.; Guarneri, A.; Guzzardi, M.A.; et al. Dapagliflozin treatment is associated with a reduction of epicardial adipose tissue thickness and epicardial glucose uptake in human type 2 diabetes. Cardiovasc. Diabetol. 2023, 22, 349. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Diaz-Rodriguez, E.; Agra, R.M.; Fernandez, A.L.; Adrio, B.; Garcia-Caballero, T.; Gonzalez-Juanatey, J.R.; Eiras, S. Effects of dapagliflozin on human epicardial adipose tissue: Modulation of insulin resistance, inflammatory chemokine production, and differentiation ability. Cardiovasc. Res. 2018, 114, 336–346. [Google Scholar] [PubMed]
- Sato, T.; Aizawa, Y.; Yuasa, S.; Kishi, S.; Fuse, K.; Fujita, S.; Ikeda, Y.; Kitazawa, H.; Takahashi, M.; Sato, M.; et al. The effect of dapagliflozin treatment on epicardial adipose tissue volume. Cardiovasc. Diabetol. 2018, 17, 6. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bao, Y.; Hu, Y.; Shi, M.; Zhao, Z. SGLT2 inhibitors reduce epicardial adipose tissue more than GLP-1 agonists or exercise interventions in patients with type 2 diabetes mellitus and/or obesity: A systematic review and network meta-analysis. Diabetes Obes. Metab. 2025, 27, 1096–1112. [Google Scholar] [PubMed]
- Verma, S.; McMurray, J.J.V. SGLT2 inhibitors and mechanisms of cardiovascular benefit: A state-of-the-art review. Diabetologia 2018, 61, 2108–2117. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lau, D.C.; Dhillon, B.; Yan, H.; Szmitko, P.E.; Verma, S. Adipokines: Molecular links between obesity and atheroslcerosis. Am. J. Physiol. Heart Circ. Physiol. 2005, 288, H2031–H2041. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Garvey, W.T.; Van Gaal, L.; Leiter, L.A.; Vijapurkar, U.; List, J.; Cuddihy, R.; Ren, J.; Davies, M.J. Effects of canagliflozin versus glimepiride on adipokines and inflammatory biomarkers in type 2 diabetes. Metabolism 2018, 85, 32–37. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Hirst, J.A.; Farmer, A.J.; Dyar, A.; Lung, T.W.; Stevens, R.J. Estimating the effect of sulfonylurea on HbA1c in diabetes: A systematic review and meta-analysis. Diabetologia 2013, 56, 973–984. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Forst, T.; Hanefeld, M.; Jacob, S.; Moeser, G.; Schwenk, G.; Pfützner, A.; Haupt, A. Association of sulphonylurea treatment with all-cause and cardiovascular mortality: A systematic review and meta-analysis of observational studies. Diabetes Vasc. Dis. Res. 2013, 10, 302–314. [Google Scholar] [CrossRef] [Scilit]
- Gerich, J.; Raskin, P.; Jean-Louis, L.; Purkayastha, D.; Baron, M.A. PRESERVE-beta: Two-year efficacy and safety of initial combination therapy with nateglinide or glyburide plus metformin. Diabetes Care 2005, 28, 2093–2099. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Petersen, M.C.; Shulman, G.I. Mechanisms of Insulin Action and Insulin Resistance. Physiol. Rev. 2018, 98, 2133–2223. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dimitriadis, G.; Mitrou, P.; Lambadiari, V.; Maratou, E.; Raptis, S.A. Insulin effects in muscle and adipose tissue. Diabetes Res. Clin. Pract. 2011, 93, S52–S59. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nichols, G.A.; Koro, C.E.; Gullion, C.M.; Ephross, S.A.; Brown, J.B. The incidence of congestive heart failure associated with antidiabetic therapies. Diabetes Metab. Res. Rev. 2005, 21, 51–57. [Google Scholar] [PubMed]
- Marchington, J.; Pond, C. Site-specific properties of pericardial and epicardial adipose tissue: The effects of insulin and high-fat feeding on lipogenesis and the incorporation of fatty acids in vitro. Int. J. Obes. 1990, 14, 1013–1022. [Google Scholar] [PubMed]
- Trabzon, G.; Güngör, Ş.; Güllü, Ş.D.; Çalışkan, O.F.; Güllü, U.U. Evaluation of epicardial adipose tissue in children with type 1 diabetes. Pediatr. Res. 2025, 97, 311–314. [Google Scholar] [PubMed]
- Tiwari, S.; Riazi, S.; Ecelbarger, C.A. Insulin’s impact on renal sodium transport and blood pressure in health, obesity, and diabetes. Am. J. Physiol. Ren. Physiol. 2007, 293, F974–F984. [Google Scholar] [CrossRef] [Scilit]
- Elisha, B.; Azar, M.; Taleb, N.; Bernard, S.; Iacobellis, G.; Rabasa-Lhoret, R. Body Composition and Epicardial Fat in Type 2 Diabetes Patients Following Insulin Detemir Versus Insulin Glargine Initiation. Horm. Metab. Res. 2016, 48, 42–47. [Google Scholar] [PubMed]
- Soucek, F.; Covassin, N.; Singh, P.; Ruzek, L.; Kara, T.; Suleiman, M.; Lerman, A.; Koestler, C.; Friedman, P.A.; Lopez-Jimenez, F.; et al. Effects of atorvastatin (80 mg) therapy on quantity of epicardial adipose tissue in patients undergoing pulmonary vein isolation for atrial fibrillation. Am. J. Cardiol. 2015, 116, 1443–1446. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cho, K.I.; Kim, B.J.; Cha, T.J.; Heo, J.H.; Kim, H.S.; Lee, J.W. Impact of duration and dosage of statin treatment and epicardial fat thickness on the recurrence of atrial fibrillation after electrical cardioversion. Heart Vessel. 2015, 30, 490–497. [Google Scholar]
- Yamada, Y.; Takeuchi, S.; Yoneda, M.; Ito, S.; Sano, Y.; Nagasawa, K.; Matsuura, N.; Uchinaka, A.; Murohara, T.; Nagata, K. Atorvastatin reduces cardiac and adipose tissue inflammation in rats with metabolic syndrome. Int. J. Cardiol. 2017, 240, 332–338. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Alexopoulos, N.; Melek, B.H.; Arepalli, C.D.; Hartlage, G.R.; Chen, Z.; Kim, S.; Stillman, A.E.; Raggi, P. Effect of intensive versus moderate lipid-lowering therapy on epicardial adipose tissue in hyperlipidemic post-menopausal women: A substudy of the BELLES trial (Beyond Endorsed Lipid Lowering with EBT Scanning). J. Am. Coll. Cardiol. 2013, 61, 1956–1961. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Abe, M.; Matsuda, M.; Kobayashi, H.; Miyata, Y.; Nakayama, Y.; Komuro, R.; Fukuhara, A.; Shimomura, I. Effects of statins on adipose tissue inflammation: Their inhibitory effect on MyD88-independent IRF3/IFN-beta pathway in macrophages. Arterioscler. Thromb. Vasc. Biol. 2008, 28, 871–877. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Busnelli, M.; Manzini, S.; Froio, A.; Vargiolu, A.; Cerrito, M.G.; Smolenski, R.T.; Giunti, M.; Cinti, A.; Zannoni, A.; Leone, B.E.; et al. Diet induced mild hypercholesterolemia in pigs: Local and systemic inflammation, effects on vascular injury-rescue by high-dose statin treatment. PLoS ONE 2013, 8, e80588. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Horiuchi, Y.; Hirayama, S.; Soda, S.; Seino, U.; Kon, M.; Ueno, T.; Idei, M.; Hanyu, O.; Tsuda, T.; Ohmura, H.; et al. Statin therapy reduces inflammatory markers in hypercholesterolemic patients with high baseline levels. J. Atheroscler. Thromb. 2010, 17, 722–729. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bonnet, J.; McPherson, R.; Tedgui, A.; Simoneau, D.; Nozza, A.; Martineau, P.; Davignon, J.; CAP Investigators. Comparative effects of 10-mg versus 80-mg Atorvastatin on high-sensitivity C-reactive protein in patients with stable coronary artery disease: Results of the CAP (Comparative Atorvastatin Pleiotropic effects) study. Clin. Ther. 2008, 30, 2298–2313. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- González, N.; Moreno-Villegas, Z.; González Bris, A.; Egido, J.; Lorenzo, Ó. Regulation of visceral and epicardial adipose tissue for preventing car diovascular injuries associated to obesity and dia betes. Cardiovasc. Diabetol. 2017, 16, 44. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, C.K.; Yeh, C.F.; Chiang, J.Y.; Lin, T.T.; Wu, Y.F.; Chiang, C.K.; Kao, T.W.; Hung, K.Y.; Huang, J.W. Effects of atorvastatin treatment on left ventricular diastolic function in peritoneal dialysis patients-the ALEVENT clinical trial. J. Clin. Lipidol. 2017, 11, 657–666. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Beck, A.L.; Otto, M.E.; D’Avila, L.B.; Netto, F.M.; Armendaris, M.K.; Sposito, A.C. Diastolic function parameters are improved by the addition of sim vastatin to enalapril-based treatment in hyper tensive individuals. Atherosclerosis 2012, 222, 444–448. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Li, J.J.; Zheng, X.; Li, J. Statins may be beneficial for patients with slow coronary flow syndrome due to its anti-inflammatory property. Med. Hypotheses 2007, 69, 333–337. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Choi, S.Y.; Park, J.S.; Roh, M.S.; Kim, C.R.; Kim, M.H.; Serebruany, V. Inhibition of angiotensin II-Induced cardiac fibrosis by atorvastatin in adiponectin knockout mice. Lipids 2017, 52, 415–422. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, M.; Li, H.; Wang, G.; Shen, X.; Zhao, S.; Su, W. Atorvastatin prevents advanced glycation end products (AGEs)-induced cardiac fibrosis via activating peroxisome proliferator-activated receptor gamma (PPAR-g). Metabolism 2016, 65, 441–453. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Akahori, H.; Tsujino, T.; Naito, Y.; Matsumoto, M.; Sasaki, N.; Iwasaku, T.; Eguchi, A.; Sawada, H.; Hirotani, S.; Masuyama, T. Atorvastatin ameliorates cardiac fibrosis and improves left ventricular diastolic function in hypertensive diastolic heart failure model rats. J. Hypertens. 2014, 32, 1534–1541. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yamamoto, C.; Fukuda, N.; Jumabay, M.; Saito, K.; Matsumoto, T.; Ueno, T.; Soma, M.; Matsumoto, K.; Shimosawa, T. Protective effects of statin on cardiac fibrosis and apoptosis in adrenomedullin-knockout mice treated with angiotensin II and high salt loading. Hypertens. Res. 2011, 34, 348–353. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, Y.; Ohmori, K.; Mizukawa, M.; Yoshida, J.; Zeng, Y.; Zhang, L.; Shinomiya, K.; Kosaka, H.; Kohno, M. Differential impact of atorvastatin vs pravastatin on progressive insulin resistance and left ventricular diastolic dysfunction in a rat model of type II diabetes. Circ. J. 2007, 71, 144–152. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yang, X.; Xiong, T.; Ning, D.; Wang, T.; Zhong, H.; Tang, S.; Mao, Y.; Zhu, G.; Wang, D. Long-term atorvastatin or the combination of atorvastatin and nicotinamide ameliorate insulin resistance and left ventricular diastolic dysfunction in a murine model of obesity. Toxicol. Appl. Pharmacol. 2020, 402, 115132. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Werida, R.; Khairat, I.; Khedr, N.F. Effect of atorvastatin versus rosuvastatin on inflammatory biomarkers and LV function in type 2 diabetic patients with dyslipidemia. Biomed. Pharmacother. 2021, 135, 111179. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Qie, L.; Meng, X.; Wang, Y.; Feng, M.; Zhong, M.; Li, L. Assessment of regional systolic and diastolic functions affected by atorvastatin in coronary artery disease using tissue Doppler imaging. Clin. Cardiol. 2008, 31, 551–555. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Preiss, D.; Campbell, R.T.; Murray, H.M.; Ford, I.; Packard, C.J.; Sattar, N.; Rahimi, K.; Colhoun, H.M.; Waters, D.D.; LaRosa, J.C.; et al. The effect of statin therapy on heart failure events: A collaborative meta-analysis of unpublished data from major randomized trials. Eur. Heart J. 2015, 36, 1536–1546. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Fukuta, H.; Goto, T.; Wakami, K.; Ohte, N. The effect of statins on mortality in heart failure with preserved ejection fraction: A meta-analysis of propensity score analyses. Int. J. Cardiol. 2016, 214, 301–306. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Liu, G.; Zheng, X.X.; Xu, Y.L.; Ru, J.; Hui, R.T.; Huang, X.H. Meta-analysis of the effect of statins on mortality in patients with preserved ejection fraction. Am. J. Cardiol. 2014, 113, 1198–1204. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Nochioka, K.; Sakata, Y.; Miyata, S.; Miura, M.; Takada, T.; Tadaki, S.; Ushigome, R.; Yamauchi, T.; Takahashi, J.; Shimokawa, H. CHART-2 Investigators. Prognostic impact of statin use in patients with heart failure and preserved ejection fraction. Circ. J. 2015, 79, 574–582. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ashton, E.; Windebank, E.; Skiba, M.; Reid, C.; Schneider, H.; Rosenfeldt, F.; Tonkin, A.; Krum, H. Why did high-dose rosuvastatin not improve cardiac remodeling in chronic heart failure? Mechanistic insights from the UNIVERSE study. Int. J. Cardiol. 2011, 146, 404–407. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kjekshus, J.; Apetrei, E.; Barrios, V.; Böhm, M.; Cleland, J.G.; Cornel, J.H.; Dunselman, P.; Fonseca, C.; Goudev, A.; Grande, P.; et al. Rosuvastatin in older patients with systolic heart failure. N. Engl. J. Med. 2007, 357, 2248–2261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Jamialahmadi, T.; Simental-Mendia, L.E.; Eid, A.H.; Almahmeed, W.; Salehabadi, S.; Al-Rasadi, K.; Banach, M.; Sahebkar, A. Efficacy of statin therapy in reducing epicardial adipose tissue: A systematic review and meta-analysis. Arch. Med. Sci. 2024, 20, 997–1001. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- German, C.A.; Liao, J.K. Understanding the molecular mechanisms of statin pleiotropic effects. Arch. Toxicol. 2023, 97, 1529–1545. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Parisi, V.; Petraglia, L.; D’Esposito, V.; Cabaro, S.; Rengo, G.; Caruso, A.; Grimaldi, M.G.; Baldascino, F.; De Bellis, A.; Vitale, D.; et al. Statin therapy modulates thickness and inflammatory profile of human epicardial adipose tissue. Int. J. Cardiol. 2019, 274, 326–330. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Stary, H.C.; Blankenhorn, D.H.; Chandler, A.B.; Glagov, S.; Insull, W., Jr.; Richardson, M.; Rosenfeld, M.E.; Schaffer, S.A.; Schwartz, C.J.; Wagner, W.D. A definition of the intima of human arteries and of its atherosclerosis-prone regions. A report from the Committee on Vascular Lesions of the Council on Arteriosclerosis, American Heart Association. Arterioscler. Thromb. Vasc. Biol. 1992, 12, 120–134. [Google Scholar] [CrossRef] [Scilit]
- Ran, C.Q.; He, W.T. Epicardial Adipose Tissue: A Potential Target to Improve Left Ventricular Diastolic Dysfunction. Rev. Cardiovasc. Med. 2025, 26, 39224. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Dozio, E.; Ruscica, M.; Vianello, E.; Macchi, C.; Sitzia, C.; Schmitz, G.; Tacchini, L.; Corsi Romanelli, M.M. PCSK9 Expression in Epicardial Adipose Tissue: Molecular Association with Local Tissue Inflammation. Mediat. Inflamm. 2020, 2020, 1348913. [Google Scholar] [CrossRef] [Scilit]
- Rivas Galvez, R.E.; Morales Portano, J.D.; Trujillo Cortes, R.; Gomez Alvarez, E.B.; Sanchez Cubias, S.M.; Zelaya, S.M. Reduction of epicardial adipose tissue thickness with PCSK9 inhibitors. Eur. Heart J. 2020, 41, ehaa946.3008. [Google Scholar] [CrossRef] [Scilit]
- Malavazos, A.E.; Ermetici, F.; Cereda, E.; Coman, C.; Locati, M.; Morricone, L.; Corsi, M.M.; Ambrosi, B. Epicardial fat thickness: Relationship with plasma visfatin and plasminogen activator inhibitor-1 levels in visceral obesity. Nutr. Metab. Cardiovasc. Dis. 2008, 18, 523–530. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Maheswari, G.; Yamini, B.; Guru, A.; Velayutham, M.; Dhandapani, V.E.; Karuppiah, K.; Amalorpavanaden, N.D. Trimetazidine with an adjuvant therapy to normalize the circulating visfatin concentration: Future perspective and mechanistic strategies. J. King Saud. Univ.–Sci. 2023, 35, 102950. [Google Scholar] [CrossRef] [Scilit]
- Chrusciel, P.; Rysz, J.; Banach, M. Defining the role of trimetazidine in the treatment of cardiovascular disorders: Some insights on its role in heart failure and peripheral artery disease. Drugs 2014, 74, 971–980. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Salazar, J.; Luzardo, E.; Mejías, J.C.; Rojas, J.; Ferreira, A.; Rivas-Ríos, J.R.; Bermúdez, V. Epicardial Fat: Physiological, Pathological, and Therapeutic Implications. Cardiol. Res. Pract. 2016, 2016, 1291537. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Patel, V.B.; Basu, R.; Oudit, G.Y. ACE2/Ang 1-7 axis: A critical regulator of epicardial adipose tissue inflammation and cardiac dysfunction in obesity. Adipocyte 2016, 5, 306–311. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Shah, S.A.; Echols, J.T.; Sun, C.; Wolf, M.J.; Epstein, F.H. Accelerated fatty acid composition MRI of epicardial adipose tissue: Development and application to eplerenone treatment in a mouse model of obesity-induced coronary microvascular disease. Magn. Reson. Med. 2022, 88, 1734–1747. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Guo, C.; Ricchiuti, V.; Lian, B.Q.; Yao, T.M.; Coutinho, P.; Romero, J.R.; Li, J.; Williams, G.H.; Adler, G.K. Mineralocorticoid receptor blockade reverses obesity related changes in expression of adiponectin, peroxisome proliferator-activated receptor gamma, and proinflammatory adipokines. Circulation 2008, 117, 2253–2261. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wada, T.; Ishikawa, A.; Watanabe, E.; Nakamura, Y.; Aruga, Y.; Hasegawa, H.; Onogi, Y.; Honda, H.; Nagai, Y.; Takatsu, K.; et al. Eplerenone prevented obesity-induced inflammasome activation and glucose intolerance. J. Endocrinol. 2017, 235, 179–191. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Olivier, A.; Pitt, B.; Girerd, N.; Lamiral, Z.; Machu, J.L.; McMurray, J.J.V.; Swedberg, K.; van Veldhuisen, D.J.; Collier, T.J.; Pocock, S.J.; et al. Effect of eplerenone in patients with heart failure and reduced ejection fraction: Potential effect modification by abdominal obesity: Insight from the EMPHASIS-HF trial. Eur. J. Heart Fail. 2017, 19, 1186–1197. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Mitchell, C.S.; Premaratna, S.D.; Bennett, G.; Lambrou, M.; Stahl, L.A.; Jois, M.; Barber, E.; Antoniadis, C.P.; Woods, S.C.; Cameron-Smith, D.; et al. Inhibition of the Renin-Angiotensin System Reduces Gene Expression of Inflammatory Mediators in Adipose Tissue Independent of Energy Balance. Front. Endocrinol. 2021, 12, 682726. [Google Scholar] [CrossRef] [Scilit]
- Anand, I.; Claggett, B.; Liu, J.; Shah, A.M.; Rector, T.S.; Shah, S.J.; Desai, A.S.; O’meara, E.; Fleg, J.L.; Pfeffer, M.A.; et al. Interaction Between Spironolactone and Natriuretic Peptides in Patients with Heart Failure and Preserved Ejection Fraction: From the TOPCAT Trial. JACC Heart Fail. 2017, 5, 241–252. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Anand, I.S.; Rector, T.S.; Cleland, J.G.; Kuskowski, M.; McKelvie, R.S.; Persson, H.; McMurray, J.J.; Zile, M.R.; Komajda, M.; Massie, B.M.; et al. Prognostic value of baseline plasma amino-terminal pro-brain natriuretic peptide and its interactions with irbesartan treatment effects in patients with heart failure and preserved ejection fraction: Findings from the I-PRESERVE trial. Circ. Heart Fail. 2011, 4, 569–577. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moro, C.; Klimcakova, E.; Lolmède, K.; Berlan, M.; Lafontan, M.; Stich, V.; Bouloumié, A.; Galitzky, J.; Arner, P.; Langin, D. Atrial natriuretic peptide inhibits the production of adipokines and cytokines linked to inflammation and insulin resistance in human subcutaneous adipose tissue. Diabetologia 2007, 50, 1038–1047. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Bae, C.R.; Hino, J.; Hosoda, H.; Arai, Y.; Son, C.; Makino, H.; Tokudome, T.; Tomita, T.; Kimura, T.; Nojiri, T.; et al. Over expression of C-type natriuretic peptide in endothelial cells protects against insulin resistance and inflammation during diet-induced obesity. Sci. Rep. 2017, 7, 9807. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tamura, N.; Ogawa, Y.; Chusho, H.; Nakamura, K.; Nakao, K.; Suda, M.; Kasahara, M.; Hashimoto, R.; Katsuura, G.; Mukoyama, M.; et al. Cardiac fibrosis in mice lacking brain natriuretic peptide. Proc. Natl. Acad. Sci. USA. 2000, 97, 4239–4244. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Lanfear, D.E.; Chow, S.; Padhukasahasram, B.; Li, J.; Langholz, D.; Tang, W.H.; Williams, L.K.; Sabbah, H.N. Genetic and nongenetic factors influencing pharmacokinetics of B-type natriuretic peptide. J. Card. Fail 2014, 20, 662–668. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Standeven, K.F.; Hess, K.; Carter, A.M.; Rice, G.I.; Cordell, P.A.; Balmforth, A.J.; Lu, B.; Scott, D.J.; Turner, A.J.; Hooper, N.M.; et al. Neprilysin, obesity and the metabolic syndrome. Int. J. Obes. 2011, 35, 1031–1040. [Google Scholar]
- Bordicchia, M.; Ceresiani, M.; Pavani, M.; Minardi, D.; Polito, M.; Wabitsch, M.; Cannone, V.; Burnett, J.C., Jr.; Dessì-Fulgheri, P.; Sarzani, R. Insulin/glucose induces natriuretic peptide clearance receptor in human adipocytes: A metabolic link with the cardiac natriuretic pathway. Am. J. Physiol. Regul. Integr. Comp. Physiol. 2016, 311, R104–R114. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Wu, W.; Shi, F.; Liu, D.; Ceddia, R.P.; Gaffin, R.; Wei, W.; Fang, H.; Lewandowski, E.D.; Collins, S. Enhancing natriuretic peptide signaling in adipose tissue, but not in muscle, protects against diet-induced obesity and insulin resistance. Sci. Signal 2017, 10, eaam6870. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, H.J. Anti-inflammatory effects of colchicine on coronary artery disease. Cardiovasc. Prev. Pharmacother. 2022, 4, 7–12. [Google Scholar] [CrossRef] [Scilit]
- Egami, Y.; Nishino, M.; Shutta, R.; Makino, N.; Taniike, M.; Nakamura, D.; Yoshimura, T.; Mori, N.; Tanaka, A.; Morita, H.; et al. Correlation between Colchicine Effects on Early Atrial Fibrillation Recurrence after Ablation and Left Atrium Epicardial Adipose Tissue Volume. J. Am. Coll. Cardiol. 2014, 63, A442. [Google Scholar] [CrossRef] [Scilit]
- Lakshamanan, S.; Abbas, N.; Narashim, A.; Condello, M.; Kinninger, A.; Krishnan, S.; Roy, S.; Budoff, M.J. 26-A-20880-ACC The Effect of Colchicine on Epicardial Adipose Tissue by Serial CCTA: Insights from the Ekstrom Trial. J. Am. Coll. Cardiol. 2026, 87, A895. [Google Scholar] [CrossRef] [Scilit]


Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Published by MDPI on behalf of the Lithuanian University of Health Sciences. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Đuzel Čokljat, A.; Grubić Rotkvić, P.; Babić, Z.; Huljev Šipoš, I.; Bekić, M.; Njire Bratičević, M.; Rotkvić, L.; Cigrovski Berković, M. Epicardial Adipose Tissue in Diabetic Heart Disease: Impact on Cardiac Function and Modulation Strategies, a Comprehensive Review. Medicina 2026, 62, 1402. https://doi.org/10.3390/medicina62071402
Đuzel Čokljat A, Grubić Rotkvić P, Babić Z, Huljev Šipoš I, Bekić M, Njire Bratičević M, Rotkvić L, Cigrovski Berković M. Epicardial Adipose Tissue in Diabetic Heart Disease: Impact on Cardiac Function and Modulation Strategies, a Comprehensive Review. Medicina. 2026; 62(7):1402. https://doi.org/10.3390/medicina62071402
Chicago/Turabian StyleĐuzel Čokljat, Ana, Petra Grubić Rotkvić, Zdravko Babić, Ivana Huljev Šipoš, Marijo Bekić, Marina Njire Bratičević, Luka Rotkvić, and Maja Cigrovski Berković. 2026. "Epicardial Adipose Tissue in Diabetic Heart Disease: Impact on Cardiac Function and Modulation Strategies, a Comprehensive Review" Medicina 62, no. 7: 1402. https://doi.org/10.3390/medicina62071402
APA StyleĐuzel Čokljat, A., Grubić Rotkvić, P., Babić, Z., Huljev Šipoš, I., Bekić, M., Njire Bratičević, M., Rotkvić, L., & Cigrovski Berković, M. (2026). Epicardial Adipose Tissue in Diabetic Heart Disease: Impact on Cardiac Function and Modulation Strategies, a Comprehensive Review. Medicina, 62(7), 1402. https://doi.org/10.3390/medicina62071402