Hospitalized Versus Outpatient Benign Acute Childhood Myositis: A 10-Year Single-Center Experience

Abstract
1. Introduction
2. Materials and Methods
2.1. Study Design and Patient Selection
2.2. Data Collection
2.3. Virological and Metabolic Evaluation
2.4. Treatment and Follow-Up
3. Statistical Analysis
4. Results
4.1. Demographic Characteristics
4.2. Comparison of Hospitalized and Outpatient Patients
4.3. Laboratory Findings
4.4. Etiological Comparisons
4.5. Factors Associated with Hospitalization
4.6. Treatment and Outcome
5. Discussion
6. Limitation
7. Conclusions
Author Contributions
Funding
Institutional Review Board Statement
Informed Consent Statement
Data Availability Statement
Conflicts of Interest
Abbreviations
References
- Attanasi, F.; Costantino, A.; Benucci, C.; Lasagni, D.; Trapani, S. Benign acute childhood myositis: Five years’ experience in a tertiary care pediatric hospital. Eur. J. Pediatr. 2023, 182, 4341–4349. [Google Scholar] [CrossRef] [Scilit]
- Brisca, G.; Mariani, M.; Pirlo, D.; Romanengo, M.; Pistorio, A.; Gaiero, A.; Panicucci, C.; Piccotti, E.; Bruno, C. Management and outcome of benign acute childhood myositis in the pediatric emergency department. Ital. J. Pediatr. 2021, 47, 57. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Tekin, E.; Akoğlu, H.A. From influenza to SARS-CoV-2: Etiological evaluation of acute benign childhood myositis. Acta Neurol. Belg. 2022, 122, 1043–1047. [Google Scholar] [CrossRef] [Scilit]
- Pasquinucci, M.; Calgaro, A.; Scollo, M.; Meneghesso, D. Epidemiological trends in benign acute childhood myositis before and after the COVID-19 pandemic: A multicenter retrospective study. Cureus 2025, 17, e91635. [Google Scholar] [CrossRef] [Scilit]
- Alghamdi, N.A.; Ajeebi, A.A.; Alajlan, A.K.; Aldaffaa, A.Y.; Philip, W.; Hameed, T.K. Benign acute childhood myositis: A retrospective cohort study from a large tertiary care children’s hospital. Front. Pediatr. 2025, 13, 1653651. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Chen, H.W.; Chang, M.C.; Wang, T.L.; Shia, B.C.; Wang, S.R. Benign acute childhood myositis in the COVID-19 era: How does it compare to influenza? Eur. J. Pediatr. 2025, 184, 291. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Özkale, Y.; Özkale, M.; Kiper, P.; Çetinkaya, B.; Erol, İ. Sandfly fever: Two case reports. Turk. Pediatri Ars. 2016, 51, 110–113. [Google Scholar] [CrossRef] [Scilit]
- Öztürk, B.; Göktuğ, A.; Bodur, İ.; Yaradılmış, R.M.; Güneylioğlu, M.M.; Güngör, A.; Tekeli, A.; Akça Çağlar, A.; Karacan, C.D.; Tuygun, N. Benign acute childhood myositis: Factors associated with muscle symptoms and resolution. Pediatr. Int. 2022, 64, e15273. [Google Scholar] [CrossRef] [Scilit]
- Turan, C.; Yurtseven, A.; Çiçek, C.; Keskin, G.; Saz, E.U. Benign acute childhood myositis associated with influenza A/B in the pediatric emergency department and the efficacy of early-onset oseltamivir. J. Paediatr. Child Health 2022, 58, 1022–1027. [Google Scholar] [CrossRef] [Scilit]
- Costa Azevedo, A.; Costa e Silva, A.; Silva, J.C.; Poço Miranda, S.; Costa, M.; Martinho, I. Benign acute childhood myositis: A five-year retrospective study. Arch. Pediatr. 2022, 29, 490–493. [Google Scholar] [CrossRef] [Scilit]
- Jarkoc, T.; Cengić, A.; Selmanović, V.; Hadžimuhamedović, A.; Vukas, E.; Uzicanin, S.; Huseinbegovic, Z.; Sarajlić, M. Characteristics of patients with benign acute childhood myositis. Mater. Sociomed. 2025, 37, 106–110. [Google Scholar] [CrossRef] [Scilit]
- D’Amico, S.; Gangi, G.; Barbagallo, M.; Palermo, T.; Finocchiaro, M.C.; Distefano, A.; Falsaperla, R.; Marino, S.; Greco, F.; Smilari, P.; et al. Benign acute childhood myositis: Our experience on clinical evaluation. Neuropediatrics 2022, 53, 418–422. [Google Scholar] [CrossRef] [Scilit]
- Kerr, J.; Macartney, K.; Britton, P.N. Influenza-associated myositis: A single-centre, five-year retrospective study. Eur. J. Pediatr. 2021, 180, 577–584. [Google Scholar] [CrossRef] [Scilit]
- Rosenberg, T.; Heitner, S.; Scolnik, D.; Levin Ben-Adiva, E.; Rimon, A.; Glatstein, M. Outcome of benign acute childhood myositis: Experience of two large tertiary pediatric hospitals. Pediatr. Emerg. Care 2018, 34, 400–402. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kosmeri, C.; Papasavva, M.E.; Kyrkou, A.; Gketsi, V.; Siomou, E.; Ladomenou, F.; Makis, A. Influenza-associated benign acute childhood myositis during the 2024–2025 season. Children 2025, 12, 1333. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Davis, L.E.; Kornfeld, M. Experimental influenza B viral myositis. J. Neurol. Sci. 2001, 187, 61–67. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Cardin, S.P.; Martin, J.G.; Saad-Magalhães, C. Clinical and laboratory description of acute viral myositis. J. Pediatr. 2015, 91, 442–447. [Google Scholar] [CrossRef] [Scilit]
- Pradhan, S.; Das, A.; Anand, S. Benign acute childhood myositis: A benign disease mimicking severe neuromuscular disorders. J. Pediatr. Neurosci. 2018, 13, 404–409. [Google Scholar] [CrossRef] [Scilit]
- Cavagnaro, S.M.F.; Aird, G.A.; Harwardt, R.I.; Marambio, Q.C.G. Benign acute childhood myositis: Clinical series and literature review. Rev. Chil. Pediatr. 2017, 88, 268–274. [Google Scholar] [CrossRef] [Scilit]
- Brisca, G.; Mariani, M.; Bellini, T.; Cervello, C.; Di Giorgi, M.; Mesini, A.; Strati, M.F.; Pirlo, D.; Bruno, C.; Piccotti, E.; et al. Increase in benign acute childhood myositis in the post-COVID era. Eur. J. Pediatr. 2025, 184, 599. [Google Scholar] [CrossRef] [Scilit]
- Szarawarski, B.; Nowak, M.; Kula-Gradzik, J. Benign acute childhood myositis: A three-year experience from a pediatric department in Poland. Cureus 2025, 17, e93822. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Majava, E.; Renko, M.; Kuitunen, I. Benign acute childhood myositis: A scoping review of clinical presentation and viral etiology. Eur. J. Pediatr. 2024, 183, 4641–4647. [Google Scholar] [CrossRef] [Scilit]
- Zafeiriou, D.I.; Katzos, G.; Gombakis, N.; Kontopoulos, E.E.; Tsantali, C. Clinical features, laboratory findings and differential diagnosis of benign acute childhood myositis. Acta Paediatr. 2000, 89, 1493–1494. [Google Scholar] [CrossRef]
- Rajajee, S.; Ezhilarasi, S.; Rajarajan, K. Benign acute childhood myositis. Indian J. Pediatr. 2005, 72, 399–400. [Google Scholar] [CrossRef] [Scilit]
- Gündüz, B.Ö.; Ataş, E.; Ünay, B.; Halil, H. Evaluation of influenza patients admitted during the 2019–2020 flu season. J. Pediatr. Infect. Dis. 2022, 17, 76–82. [Google Scholar] [CrossRef] [Scilit]
- Szenborn, L.; Toczek-Kubicka, K.; Zaryczański, J.; Marchewka-Kowalik, M.; Miśkiewicz, K.; Kuchar, E. Benign acute childhood myositis during influenza B outbreak. In Advances in Experimental Medicine and Biology; Pokorski, M., Ed.; Springer: Cham, Switzerland, 2018; pp. 29–34. [Google Scholar] [CrossRef] [Scilit]
- Karpathios, T.; Kostaki, M.; Drakonaki, S.; Garoufi, A.; Siahanidou, S.; Spirou, N.; Theodoridis, C. Influenza B epidemic causing benign acute myositis. Eur. J. Pediatr. 1995, 154, 334–336. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Torres, P.A.; Helmstetter, J.A.; Kaye, A.M.; Kaye, A.D. Rhabdomyolysis: Pathogenesis, diagnosis, and treatment. Ochsner J. 2015, 15, 58–69. [Google Scholar] [PubMed]
- Mackay, M.T.; Kornberg, A.J.; Shield, L.K.; Dennett, X. Benign acute childhood myositis: Laboratory and clinical features. Neurology 1999, 53, 2127–2131. [Google Scholar] [CrossRef] [Scilit]
- King, B.A. Benign acute childhood myositis as a cause of failure to weight bear. J. Paediatr. Child Health 2003, 39, 378–380. [Google Scholar] [CrossRef] [Scilit]
- Agyeman, P.; Duppenthaler, A.; Heininger, U.; Aebi, C. Influenza-associated myositis in children. Infection 2004, 32, 199–203. [Google Scholar] [CrossRef] [Scilit]



| Patients (n = 93) | Mean ± SD Median (Range) |
|---|---|
| Age, years | 7.4 ± 3.3 |
| 7.0 (2.0–17.0) | |
| Sex (n, %) | |
| Female | 22 (23.7) |
| Male | 71 (76.3) |
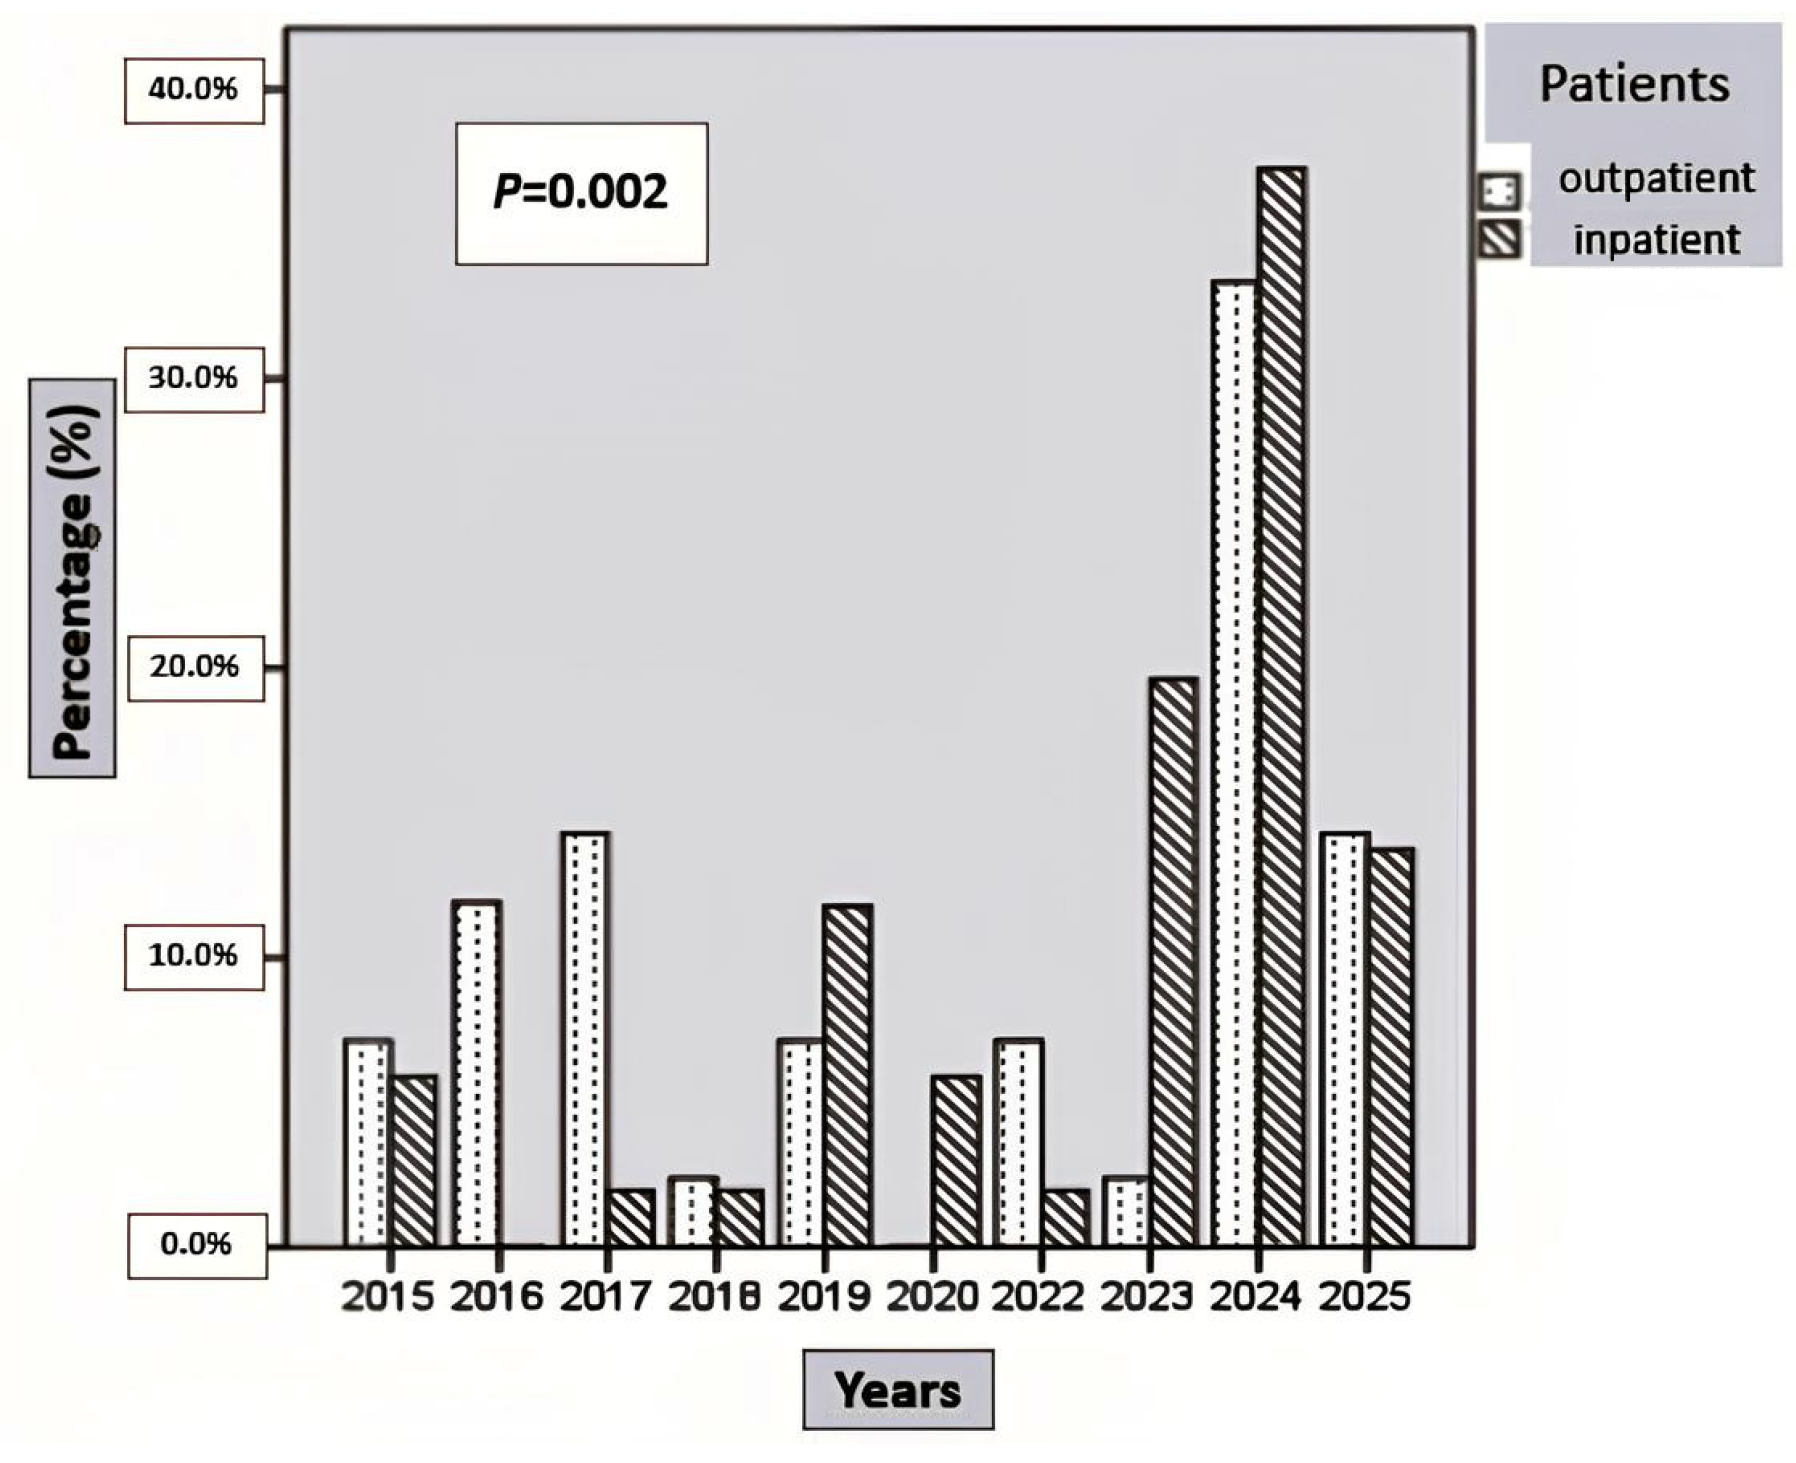
| Follow-up setting (n, %) | |
| Outpatient | 42 (45.2) |
| Inpatient ward | 48 (51.6) |
| PICU | 3 (3.2) |
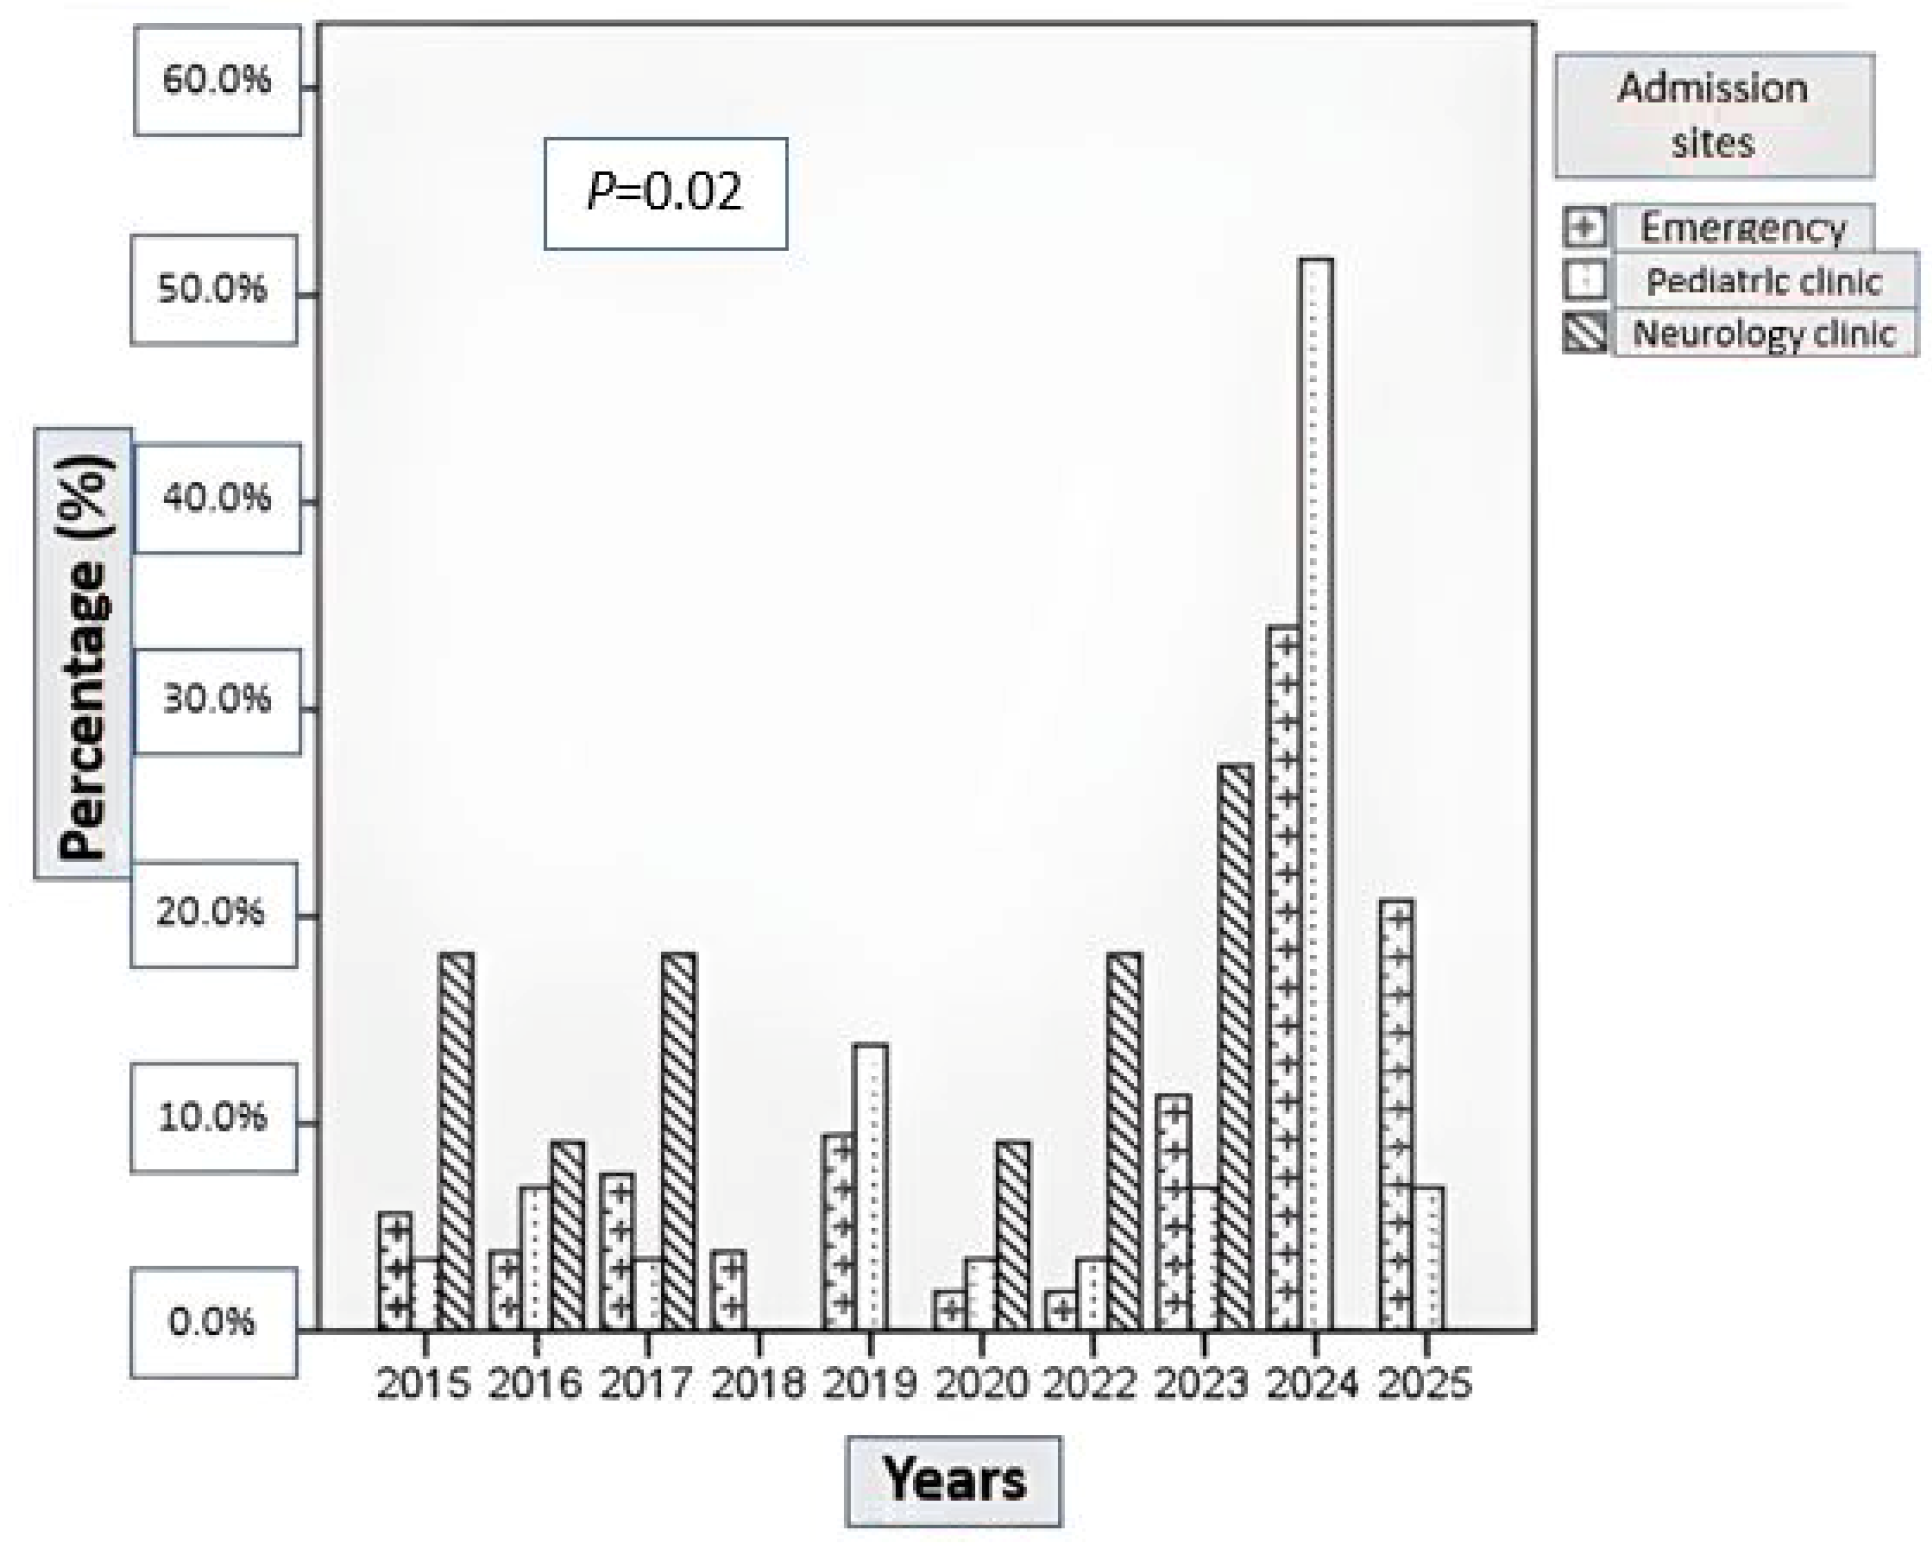
| Place of admission (n, %) | |
| ED | 53 (57.0) |
| Pediatric clinic | 29 (31.2) |
| Neurology clinic | 11 (11.8) |
| Mode of admission (n,%) | |
| Direct admission | 87 (93.5) |
| Referred admission | 6 (6.5) |
| Patients (n = 93) | |||
|---|---|---|---|
| Variable | Outpatients (n:42) | Hospitalized Patients (n:51) | p Value * |
| Age (years) Median (range) | 7.6 ± 3.4 | 7.3 ± 3.2 | 0.65 |
| Sex (n, %) Female Male | 7 (16.7) 35 (83.3) | 15 (29.4) 36 (70.6) | 0.14 |
| Duration of symptoms, days Fever Cough URTI Myalgia Inability to walk Sore throat Interval between fever onset and myalgia onset | 3.4 ± 0.2 1.5 ± 0.4 3.9 ± 0.3 1.9 ± 0.1 1.4 ± 0.1 3.4 ± 0.8 1.6 ± 0.2 | 3.4 ± 0.1 1.8 ± 0.2 3.2 ± 0.2 1.8 ± 0.1 1.3 ± 0.08 2.1 ± 0.1 1.8 ± 0.1 | 0.98 0.49 0.07 0.37 0.62 0.09 0.37 |
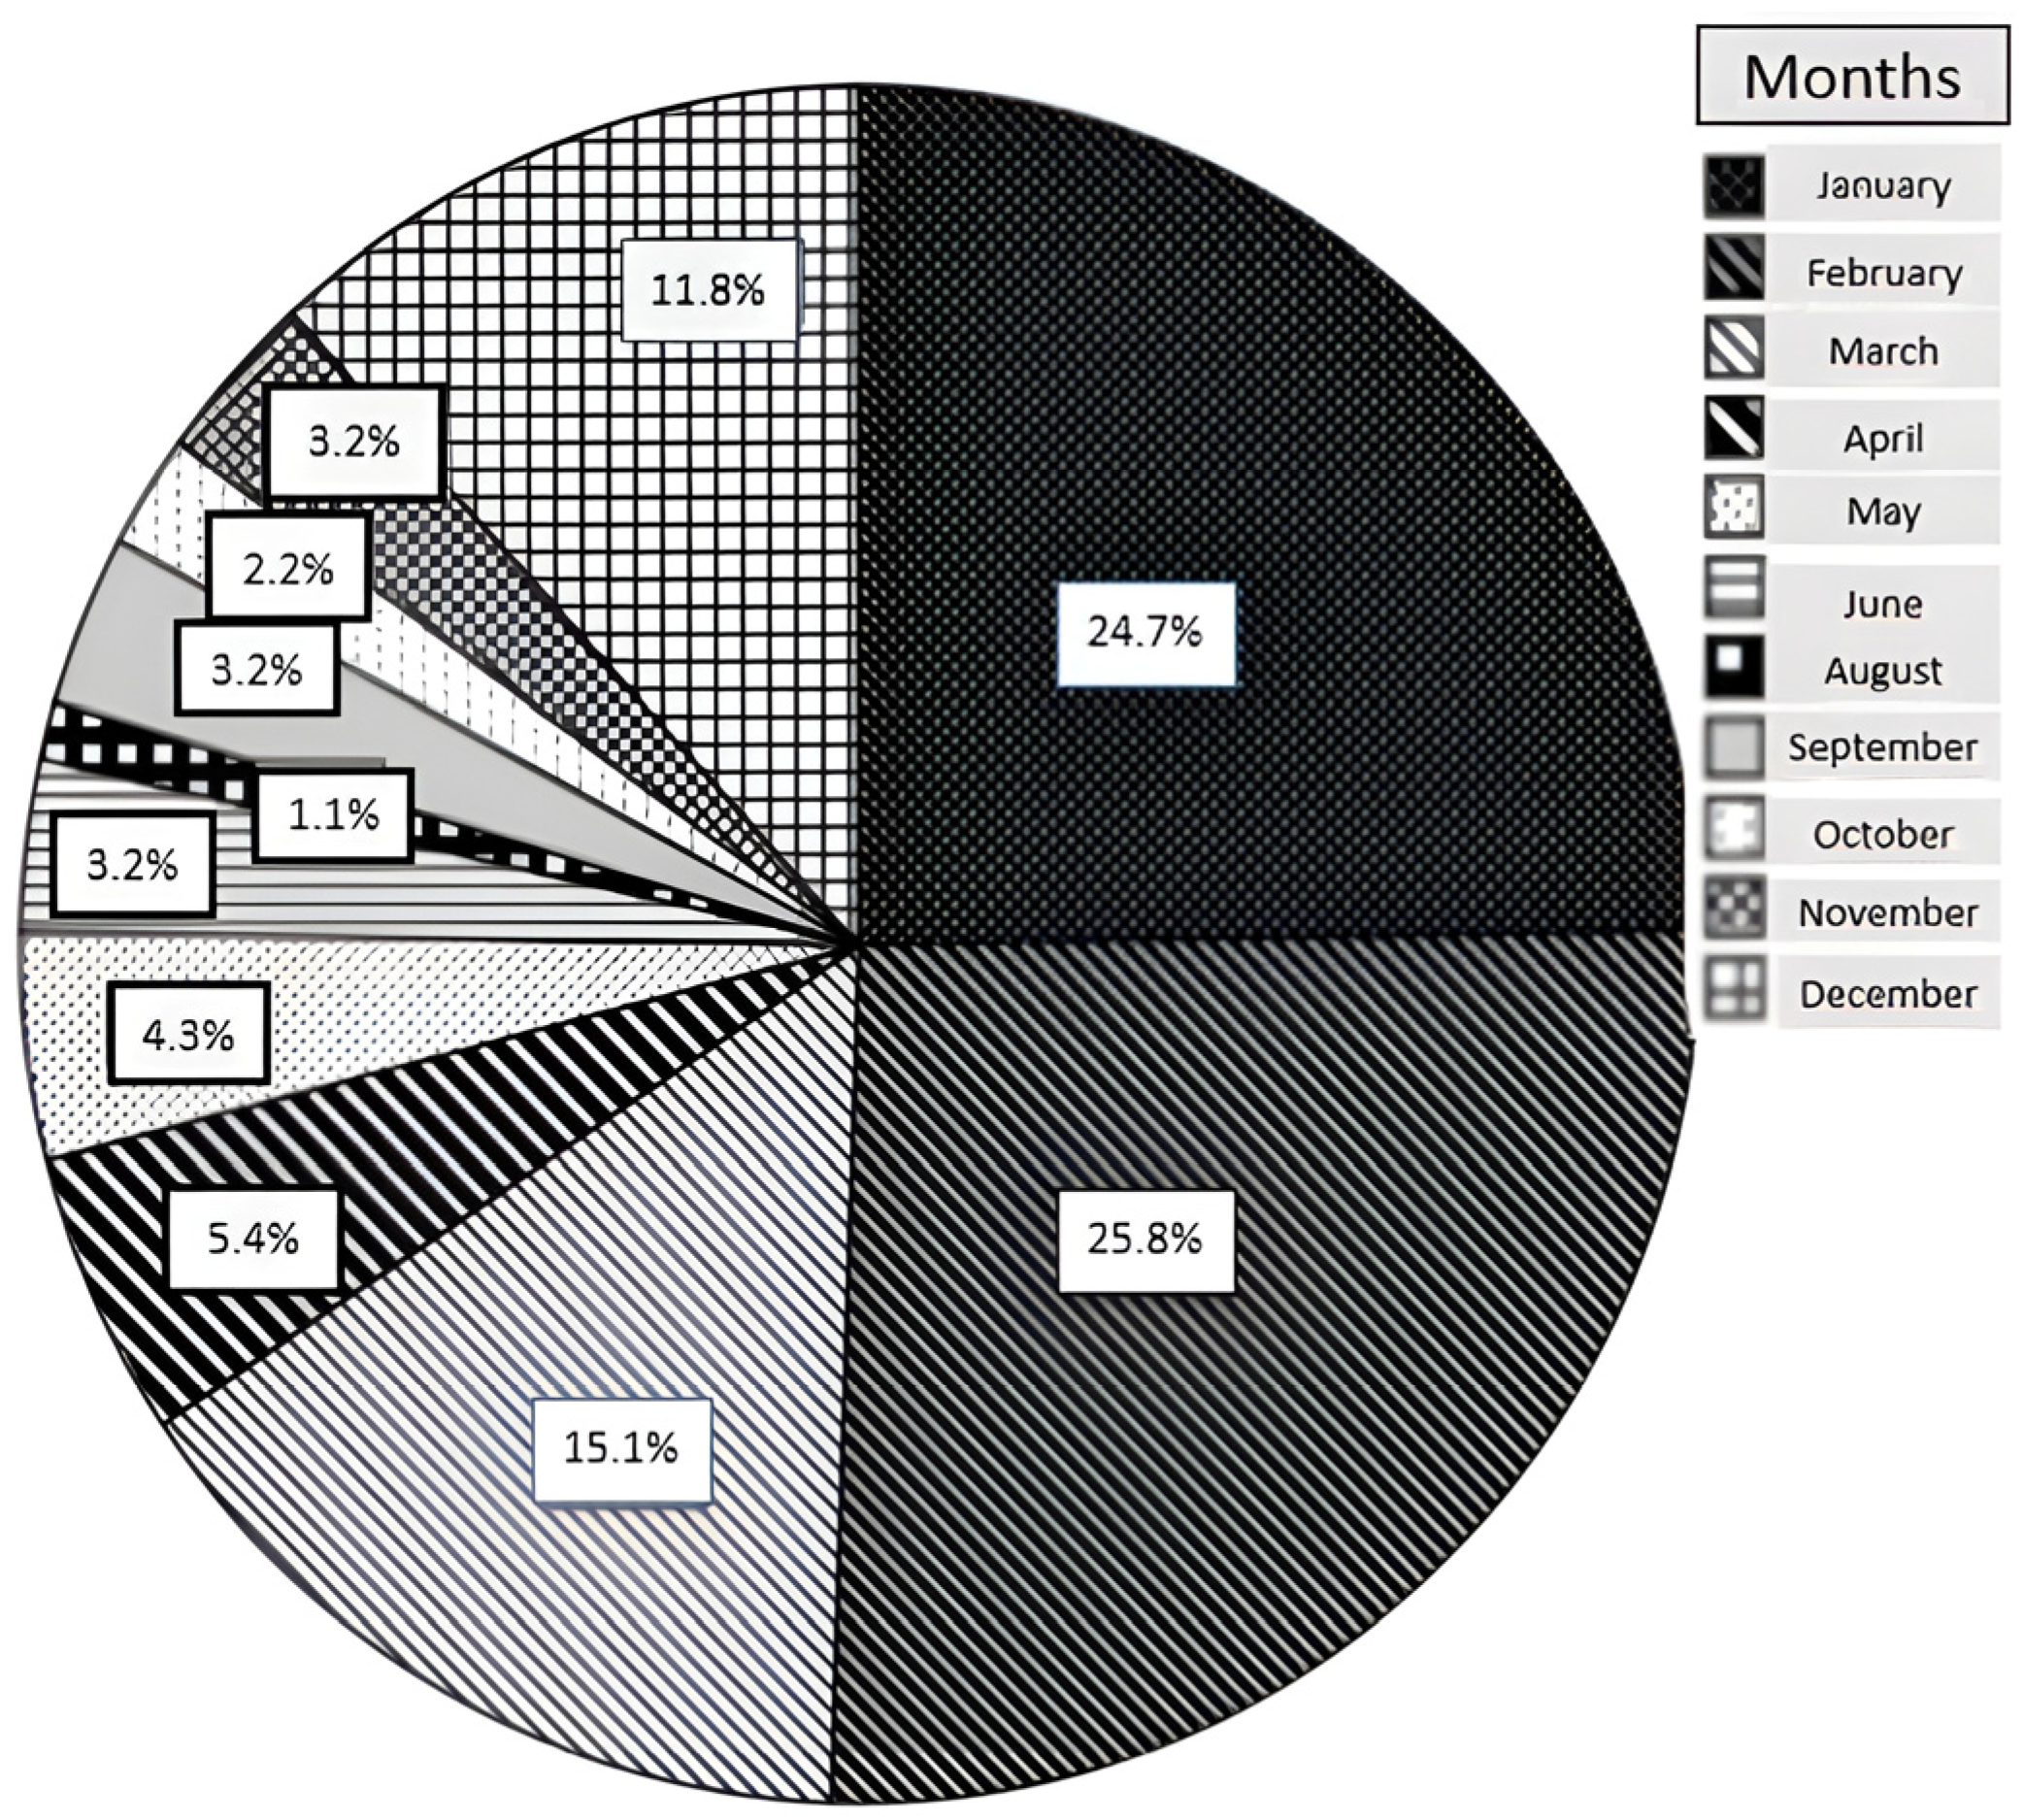
| Monthly distribution of cases (n, %) January February March April May June August September October November December | 10 (23.8) 11 (26.2) 9 (21.4) 2 (4.8) 2 (4.8) 1 (2.4) 0 (0) 1 (2.4) 2 (4.8) 0 (0) 4 (9.4) | 13 (25.5) 13 (25.5) 5 (9.8) 3 (5.9) 2 (3.9) 2 (3.9) 1 (2.0) 2 (3.9) 0 (0) 3 (5.9) 7 (13.7) | 0.37 |
| Symptoms Fever (n, %) Yes No Cough (n, %) Yes No URTI (n, %) Yes No Myalgia (n, %) Yes No Inability to Walk (n, %) Yes No Sore Throat (n, %) Yes No ** Additional Complaint (n, %) Yes No | 41 (97.6) 1 (2.4) 20 (47.6) 22 (52.4) 39 (92.9) 3 (7.1) 41 (97.6) 1 (2.4) 24 (57.1) 18 (42.9) 7 (16.7) 35 (83.3) 10 (23.8) 32 (76.2) | 50 (98.0) 1 (2.0) 21 (41.2) 30 (58.8) 48 (94.1) 3 (5.9) 51 (100.0) 0 (0) 46 (90.2) 5 (9.8) 8 (15.7) 43 (84.3) 19 (37.3) 32 (62.7) | 0.89 0.53 0.81 0.45 0.0001 * 0.90 0.16 |
| Variable | Outpatient (n = 42) | Hospitalized Patient (n = 51) | p Value |
|---|---|---|---|
| Hematological and biochemical parameters | |||
| Hb (g/dL) | 12.5 ± 1.2 | 12.6 ± 1.4 | 0.87 |
| Leukocyte (/mm3) | 5407.7 ± 387.8 | 5540.8 ± 520.8 | 0.84 |
| Lymphocyte (/mm3) | 2106.0 ± 202.9 | 2240.7 ± 160.5 | 0.59 |
| Neutrophil (/mm3) | 2629.7 ± 303.4 | 2708.0 ± 444.9 | 0.89 |
| Platelet (/mm3) | 230,309.5 ± 9771.9 | 199,806.3 ± 9894.6 | 0.02 * |
| Blood sugar (mg/dL) | 96.5 ± 10.8 | 98.8 ± 15.2 | 0.64 |
| Creatinine (mg/dL) | 0.46 ± 0.02 | 0.51 ± 0.03 | 0.15 |
| AST (U/L) (n:86) | 117.6 ± 17.7 | 249.6 ± 56.1 | 0.001 * |
| ALT (U/L) | 50.5 ± 7.0 | 89.2 ± 23.1 | 0.03 * |
| CK (U/L) | 1358.7 ± 145.5 | 10,658.6 ± 4871.6 | 0.0001 * |
| CKMB (U/L) (n:15) | - | 716.1 ± 421.1 | - |
| CRP (mg/dL) | 3.9 ± 0.7 | 4.7 ± 2.1 | 0.06 |
| LDH (U/L) (n = 23) | 433.4 ± 74.9 | 662.2 ± 185.5 | 0.53 |
| Urinalysis (n, %) Normal Abnormal | 20 (100.0) 0 (0) | 44 (95.7) 2 (4.3) | 0.48 |
| Etiological agents (n,%) VPN INFA INFB SARS-CoV-2 EBV INFA + RSV INFA + HSV SFV | 4 (18.2) 10 (45.5) 5 (22.7) 2 (9.1) 0 (0) 0 (0) 1 (4.5) 0 (0) | 20 (50.0) 6 (15.0) 6 (15.0) 4 (10.0) 1 (2.5) 1 (2.5) 0 (0) 2 (5.0) | 0.03 * |
| Complications (n,%) Rhabdomyolysis Yes No Acute renal failure (n,%) Yes No | 0 (0%) 42 (100) 0 (0) 42 (100) | 3 (5.9) 48 (94.1) 1 (2.0) 50 (98.0) | 0.24 0.54 |
Comorbidity (n,%) Pneumonia Sinusitis Febrile convulsions | 0 (0) 2 (100.0) 0 (0) | 4 (57.1) 2 (28.6) 1 (14.3) | 0.38 |
| Treatment | |||
| Oseltamivir (n,%) Yes No | 18 (42.9) 24 (57.1) | 30 (58.8) 21 (41.2) | 0.12 |
| Hydration (n,%) Yes No | 0 (0) 42 (100.0) | 49 (96.1) 2 (3.9) | 0.0001 * |
| Alkalization (n,%) Yes No | 0 (0) 42 (100) | 4 (7.8) 47 (92.2) | 0.12 |
| Hemodialysis (n,%) Yes No | 0 (0) 42 (100) | 1 (2.0) 50 (98.0) | 0.54 |
| Analgesic treatment (n,%) Yes No | 31 (73.8) 11 (26.2) | 40 (78.4) 11 (21.6) | 0.60 |
| Follow-up (mean ± SD) | |||
| Follow-up visit (days) Recovery (days) Control CK (U/L) Control leukocyte (×103/µL) | 7.9 ± 3.1 3.4 ± 1.2 130.6 ± 7.5 7227.5 ± 351.0 | 8.0 ± 3.9 4.2 ± 1.9 191.9 ± 19.7 7273.4 ± 290.5 | 0.81 0.03 * 0.01 * 0.91 |
| Recurrence (n, %) Yes No | 4 (9.5) 38 (90.5) | 7 (13.7) 44 (86.3) | 0.74 |
| Recurrence number (n:11) (n, %) 2 3 | 2 (50.0) 2 (50.0) | 7 (100) 0 (0) | 0.11 |
| Recurrence timing (years) (n, %) Within the same year 1 year ago 2 years ago | 0 (0) 1 (25.0) 3 (75.0) | 4 (57.1) 2 (28.6) 1 (14.3) | 0.04 * |
| Etiological Group | Recovery Time, Days (n = 61) | CK Level, U/L (n = 62) | Fever Duration, Days (n = 60) | Myalgia Duration, Days (n = 61) | Inability to Walk, Days (n = 46) | Interval Between Fever Onset and Myalgia Onset, Days (n = 62) |
|---|---|---|---|---|---|---|
| Mean ± SD | Mean ± SD | Mean ± SD | Mean ± SD | Mean ± SD | Mean ± SD | |
| VPN | 4.0 ± 0.3 | 3547 (451–247,440) | 3.6 ± 0.3 | 2.0 ± 0.2 | 1.2 ± 0.09 | 1.8 ± 0.2 |
| INFA | 2.9 ± 0.3 | 535.5 (235–5294) | 2.6 ± 0.2 | 1.5 ± 0.2 | 1.3 ± 0.2 | 1.1 ± 0.2 |
| INFB | 4.7 ± 1.0 | 1512 (377–51,800) | 4.2 ± 0.6 | 2.0 ± 0.4 | 1.7 ± 0.2 | 2.3 ± 0.5 |
| Others ** | 4.4 ± 0.4 | 2558 (180–7000) | 2.8 ± 0.4 | 1.3 ± 0.1 | 1.1 ± 0.1 | 1.6 ± 0.4 |
| p value | 0.07 | 0.0001 * | 0.01 * | 0.04 * | 0.18 | 0.04 * |
| Etiological Group | |||||
|---|---|---|---|---|---|
| 1 | 2 | 3 | 4 | p | |
| VPN (n = 22) | INFA (n = 16) | INFB (n = 11) | Others* (n = 11) | ||
| CK level (U/L) (n = 62) Median (range) | 3547 (451–247,440) | 535.5 (235–5294) | 1512 (377–51,800) | 2558 (180–7000) | 0.0001 * |
| p (1–2) 0.0001 * | p (1–3) 0.30 | p (1–4) 0.18 | p (2–3) 0.01 * | p (2–4) 0.08 | p (3–4) 0.58 |
| Duration of fever (days) (n = 60) | 3.6 ± 0.3 | 2.6 ± 0.2 | 4.2 ± 0.6 | 2.8 ± 0.4 | 0.01 * |
| p (1–2) 0.004 * | p (1–3) 0.55 | p (1–4) 0.06 | p (2–3) 0.02 * | p (2–4) 0.79 | p (3–4) 0.08 |
| Duration of myalgia (days) (n = 61) | 2.0 ± 0.2 | 1.5 ± 0.2 | 2.0 ± 0.4 | 1.3 ± 0.1 | 0.04 * |
| p (1–2) 0.04 * | p (1–3) 0.73 | p (1–4) 0.01 * | p (2–3) 0.19 | p (2–4) 0.45 | p (3–4) 0.07 |
| Interval between fever onset and myalgia onset (days) (n:62) | 1.8 ± 0.2 | 1.1 ± 0.2 | 2.3 ± 0.5 | 1.6 ± 0.4 | 0.04 * |
| P1–2 0.01 * | p (1–3) 0.45 | p (1–4) 0.37 | p (2–3) 0.02 * | p (2–4) 0.14 | p (3–4) 0.23 |
| Etiological Group | Recovery Days (n = 50) | CK Level (U/L) (n = 51) Median (Range) | Fever Duration (Days) (n = 49) | Myalgia Duration (Days) (n = 50) | Duration of Inability to Walk (Days) (n = 38) | Interval Between Fever Onset and Myalgia Onset (Days) (n = 51) |
|---|---|---|---|---|---|---|
| VPN | 4.0 ± 0.3 | 3547 (451–247,440) | 3.6 ± 0.3 | 2.0 ± 0.2 | 1.2 ± 0.09 | 1.8 ± 0.2 |
| INFA | 2.9 ± 0.3 | 535.5 (235–5294) | 2.6 ± 0.2 | 1.5 ± 0.2 | 1.3 ± 0.2 | 1.1 ± 0.2 |
| INFB | 4.7 ± 1.0 | 1512 (377–51,800) | 4.2 ± 0.6 | 2.0 ± 0.4 | 1.7 ± 0.2 | 2.3 ± 0.5 |
| p value | 0.04 * | 0.0001 * | 0.01 * | 0.16 | 0.19 | 0.02 * |
| Variable | B | S.E. | Wald | df | p | Exp (B) | 95% CI for Exp B |
|---|---|---|---|---|---|---|---|
| Constant | −1.024 | 0.842 | 1.477 | 1 | 0.22 | 0.359 | - |
| Age (years) | −0.143 | 0.092 | 2.400 | 1 | 0.12 | 0.867 | 0.723–1.039 |
| Sex (Male) | 0.364 | 0.786 | 0.215 | 1 | 0.64 | 1.439 | 0.309–6.711 |
| CK level (per 1000 U/L increase) | 1.000 | 0.275 | 13.272 | 1 | 0.0001 * | 2.72 | 1.00–7.39 |
| Myalgia | −0.110 | 1.374 | 0.006 | 1 | 0.93 | 0.896 | 0.061–13.248 |
| Inability to walk | 1.081 | 0.654 | 2.736 | 1 | 0.049 * | 2.948 | 0.819–10.612 |
| Variable | B | S.E. | Wald | df | p | Exp (B) | 95% CI for Exp B |
|---|---|---|---|---|---|---|---|
| Constant | −2.257 | 0.974 | 5.367 | 1 | 0.02 * | 0.105 | - |
| Age (years) | 0.090 | 0.091 | 0.966 | 1 | 0.33 | 1.094 | (0.915–1.308) |
| Sex (Male) | 0.310 | 0.769 | 0.163 | 1 | 0.69 | 1.364 | (0.302–6.157) |
| CK level | 0.000 | 0.000 | 0.039 | 1 | 0.84 | 1.000 | (1.000–1.000) |
| Myalgia | −0.497 | 1.149 | 0.149 | 1 | 0.70 | 0.608 | (0.049–7.618) |
| Inability to walk | −0.858 | 1.458 | 0.346 | 1 | 0.23 | 0.424 | (0.105–1.707) |
Disclaimer/Publisher’s Note: The statements, opinions and data contained in all publications are solely those of the individual author(s) and contributor(s) and not of MDPI and/or the editor(s). MDPI and/or the editor(s) disclaim responsibility for any injury to people or property resulting from any ideas, methods, instructions or products referred to in the content. |
© 2026 by the authors. Published by MDPI on behalf of the Lithuanian University of Health Sciences. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license.
Share and Cite
Özkale, Y.; Özkale, M.; Beşen, Ş.; Karsantıözü, T.; Aktaş, N.; Gülnar, G.Y.; Poyraz, B. Hospitalized Versus Outpatient Benign Acute Childhood Myositis: A 10-Year Single-Center Experience. Medicina 2026, 62, 583. https://doi.org/10.3390/medicina62030583
Özkale Y, Özkale M, Beşen Ş, Karsantıözü T, Aktaş N, Gülnar GY, Poyraz B. Hospitalized Versus Outpatient Benign Acute Childhood Myositis: A 10-Year Single-Center Experience. Medicina. 2026; 62(3):583. https://doi.org/10.3390/medicina62030583
Chicago/Turabian StyleÖzkale, Yasemin, Murat Özkale, Şeyda Beşen, Tuba Karsantıözü, Nihal Aktaş, Gökçe Yegül Gülnar, and Burak Poyraz. 2026. "Hospitalized Versus Outpatient Benign Acute Childhood Myositis: A 10-Year Single-Center Experience" Medicina 62, no. 3: 583. https://doi.org/10.3390/medicina62030583
APA StyleÖzkale, Y., Özkale, M., Beşen, Ş., Karsantıözü, T., Aktaş, N., Gülnar, G. Y., & Poyraz, B. (2026). Hospitalized Versus Outpatient Benign Acute Childhood Myositis: A 10-Year Single-Center Experience. Medicina, 62(3), 583. https://doi.org/10.3390/medicina62030583