


Abstract
Background and Objectives: Pancreatic cystic lesions (PCLs) are frequently incidental findings. The prevalence of PCLs is increasing, mainly due to advancements in imaging techniques, but also because of the aging of the population. PCLs comprise challenging clinical problems, as their manifestations vary from benign to malignant lesions. Therefore, the recognition of PCLs is achieved through a complex diagnostic and surveillance process, which in turn is usually long-term, invasive, and expensive. Despite the progress made in the identification of novel biomarkers in the cystic fluid that also support the differentiation of PCLs, their application in clinical practice is limited. Materials and Methods: We conducted a systematic review of the literature published in two databases, Pubmed and Embase, on biochemical biomarkers in PCLs that may be applied in the diagnostic algorithms of PCLs. Results: Eleven studies on intracystic glucose, twenty studies on intracystic carcinoembryonic antigen (CEA), and eighteen studies on other biomarkers were identified. Low levels of intracystic glucose had high sensitivity and specificity in the differentiation between mucinous and non-mucinous cystic neoplasms. Conclusions: CEA and glucose are the most widely studied fluid biochemical markers in pancreatic cystic lesions. Glucose has better diagnostic accuracy than CEA. Other biochemical biomarkers require further research.
Keywords:
pancreatic cyst; mucinous cyst; non-mucinous cyst; biomarker; glucose; CEA; pancreatic cancer 1. Introduction
Pancreatic cyst lesions (PCLs) are a heterogeneous group of lesions that are characterized by a broad spectrum of behavior, different malignant potential, as well as varying pathologic features. PCLs are frequently incidental findings. The prevalence of PCLs is currently growing, which is not only a reflection of the increased availability and accuracy of abdominal imaging techniques, but also a reflection of the aging population. Nevertheless, PCLs comprise challenging clinical problems, not only because of their increasing occurrence, but mainly because of their heterogeneous manifestations that vary from benign to malignant lesions. At the same time, pancreatic cancer is becoming an progressively common cause of cancer mortality, and a 2.3-fold rise in the global number of cases and deaths from these tumors has been reported [1].
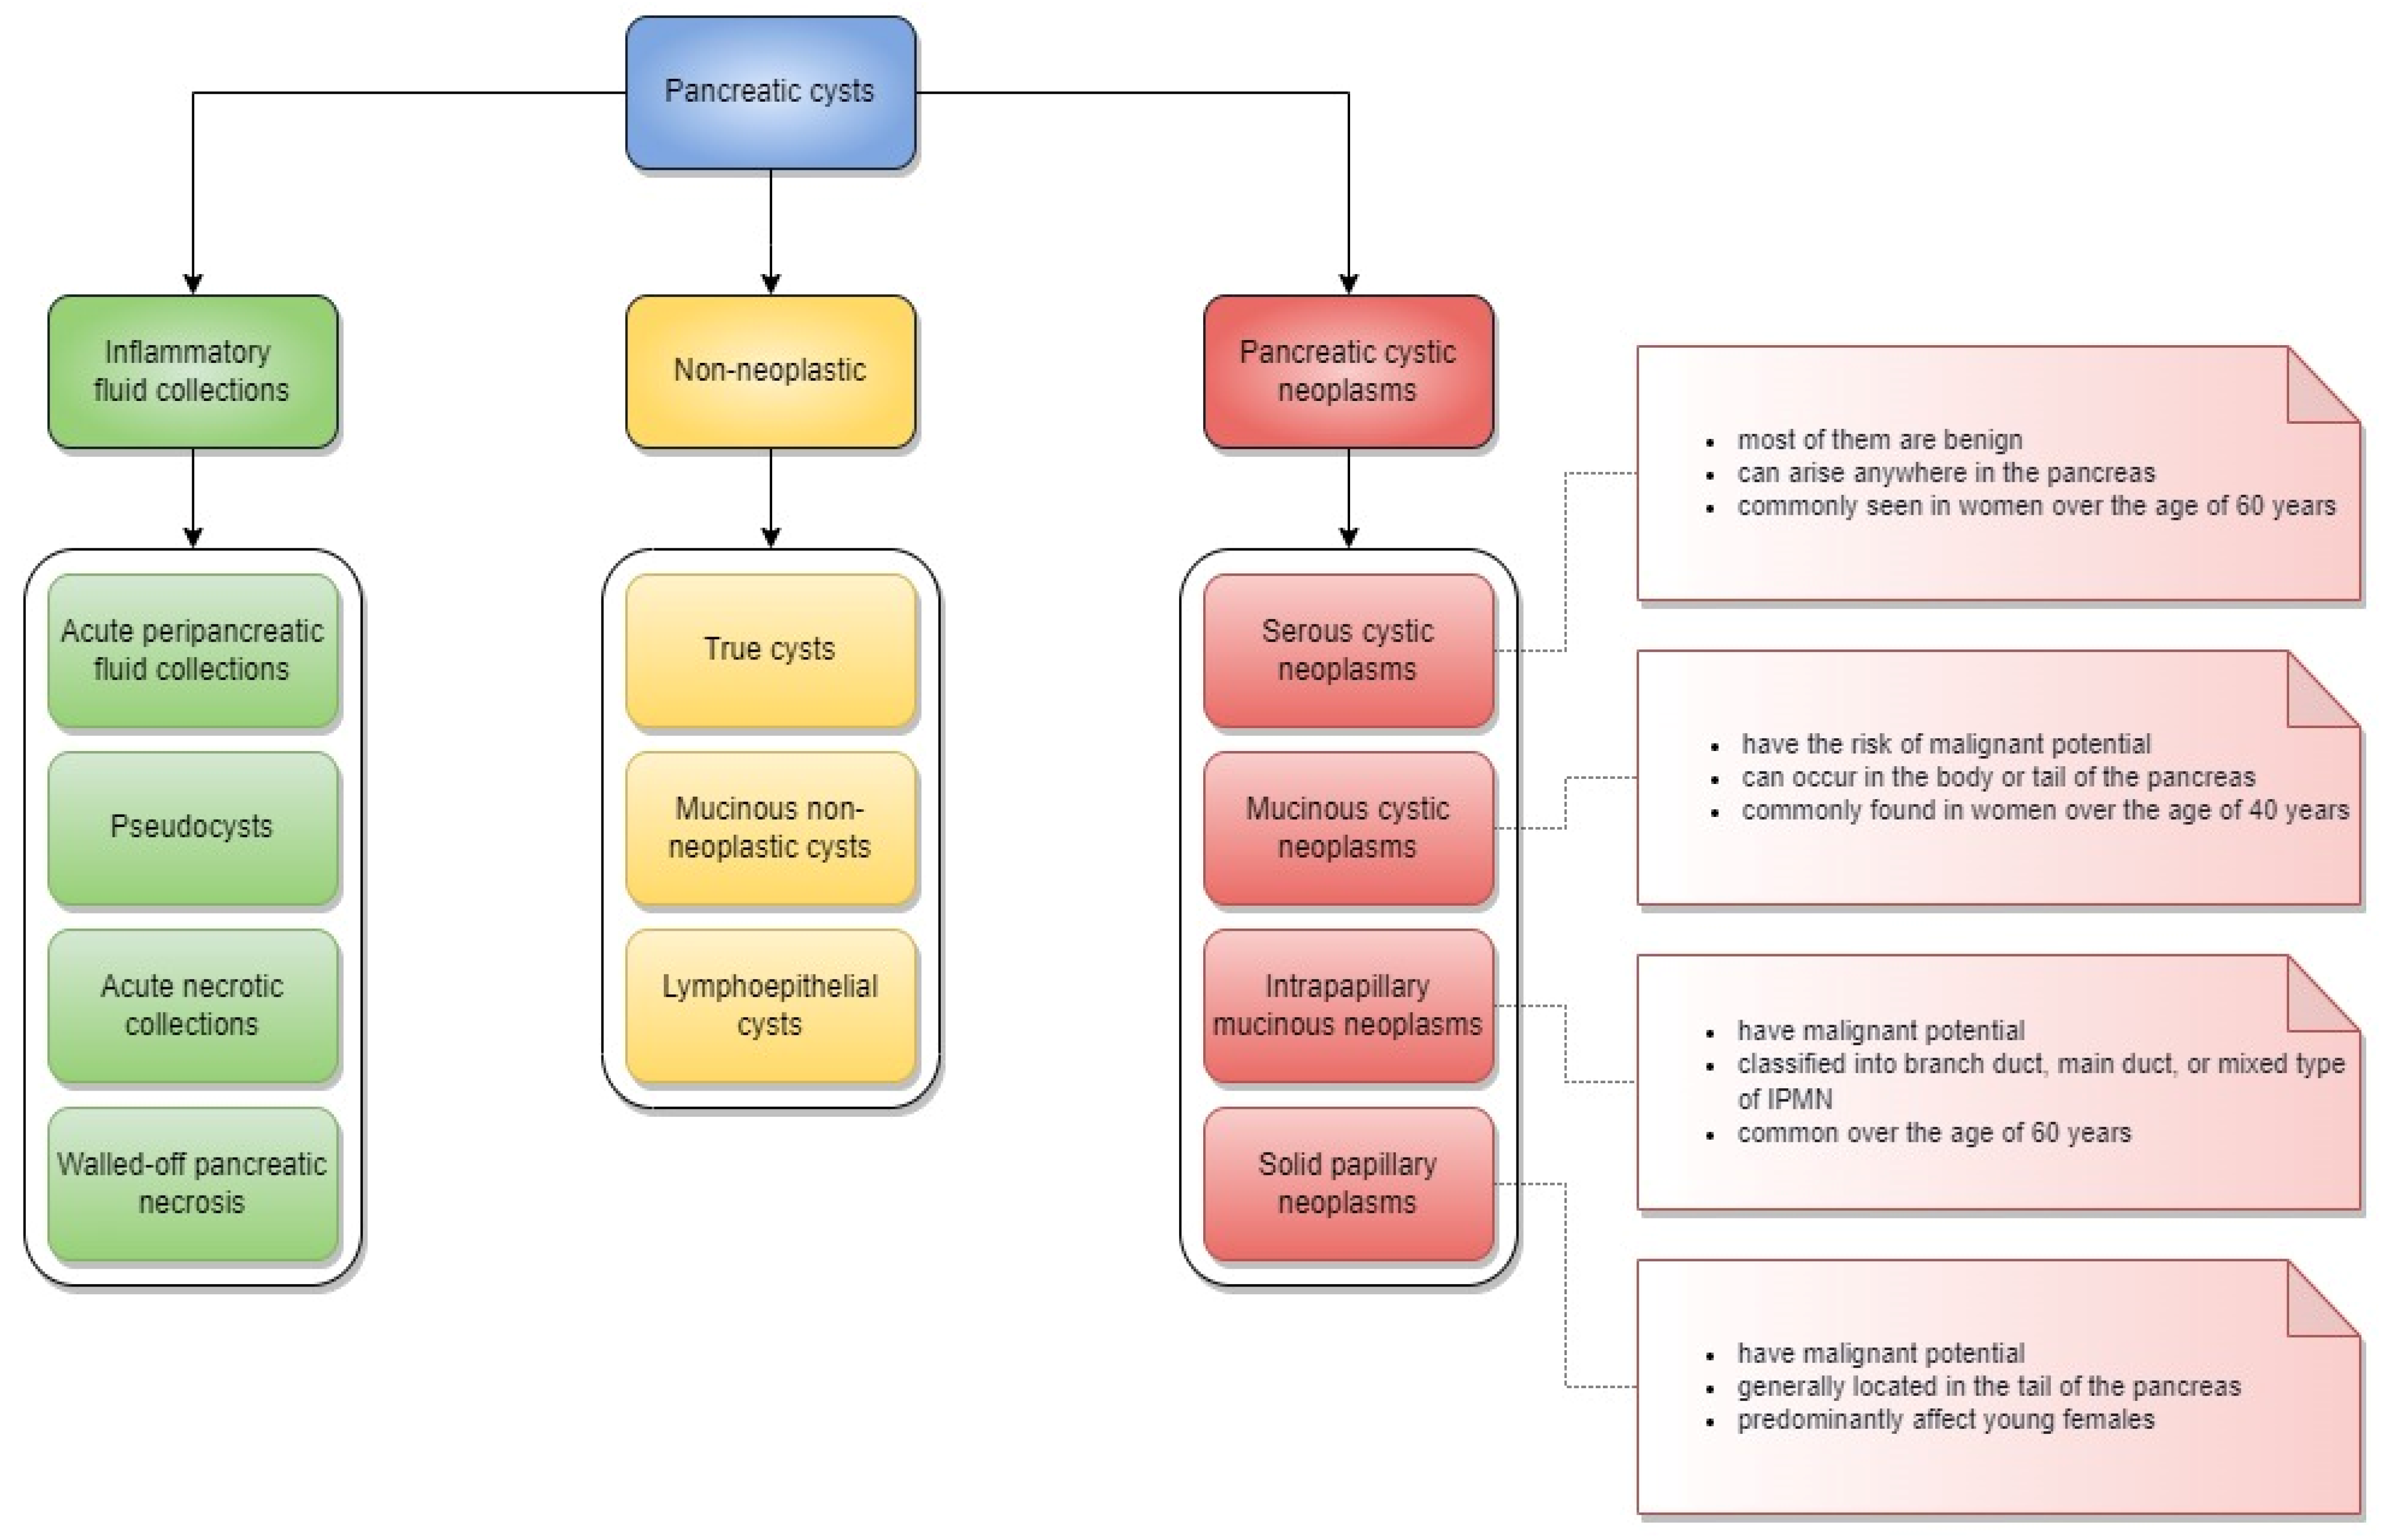
The majority of PCLs are asymptomatic, benign changes that do not require any therapeutic approach. According to their pathological classification, pancreatic cysts are classified into inflammatory fluid collections, non-neoplastic cysts, and pancreatic cystic neoplasms. Inflammatory fluid collections usually result from acute pancreatitis, and are further classified according to the Atlanta criteria into acute peripancreatic fluid collections, pseudocysts, acute necrotic collections, and walled-off pancreatic necrosis. Pancreatic cystic neoplasms (PCNs) are categorized into serous cystic tumors, mucinous cystic neoplasms (MCNs), intraductal papillary mucinous neoplasms (IPMNs), and solid pseudopapillary neoplasms (SPN). PCNs differ in morphology, which is further reflected by their varying appearance in imaging tests, clinical manifestations, and most importantly, their risk of malignant transformation [2] (Figure 1).
Figure 1.
Pathological classification of pancreatic cysts and clinical features of pancreatic cystic neoplasms. IPMN, intraductal papillary mucinous neoplasms.
Precise recognition of the type of PCL is crucial for the patient’s management. Therefore, the identification of PCLs typically initiates a complex diagnostic and surveillance process, which in turn is usually long-term, invasive, and expensive. In patients with incidentally detected pancreatic cysts, the diagnostic assessment usually includes magnetic resonance imaging (MRI) and magnetic resonance cholangiopancreatography (MRCP), which can best show if the cyst is communicating with the pancreatic duct. For instance, it has been demonstrated that the branched IPMN (BD-IPMN), even though it has malignant potential, may be less malignant compared to the IPMN of the main duct [2]. On the other hand, endoscopic ultrasonography (EUS) can complement diagnostics as the most accurate method of assessing small changes located in the head of the pancreas, enabling the assessment of the cyst structure and its puncture in order to obtain cystic fluid for cytological and biochemical examination [3]. Intracystic fluid biomarkers have an important role in the categorization of PCLs; however, their application in clinical practice is limited to carcinoembryonic antigen (CEA). According to the European evidence-based guidelines on pancreatic cystic neoplasms, assessment of cyst fluid CEA, combined with cytology, or not routinely available KRAS/GNAS mutation analyses, may be considered for differentiating an IPMN or MCN from other PCNs [4].
We conducted a systematic review of biochemical intracystic biomarkers, in order to identify the assortment of fluid indicators that may assist in the diagnostic evaluation of patients with PCLs.
2. Materials and Methods
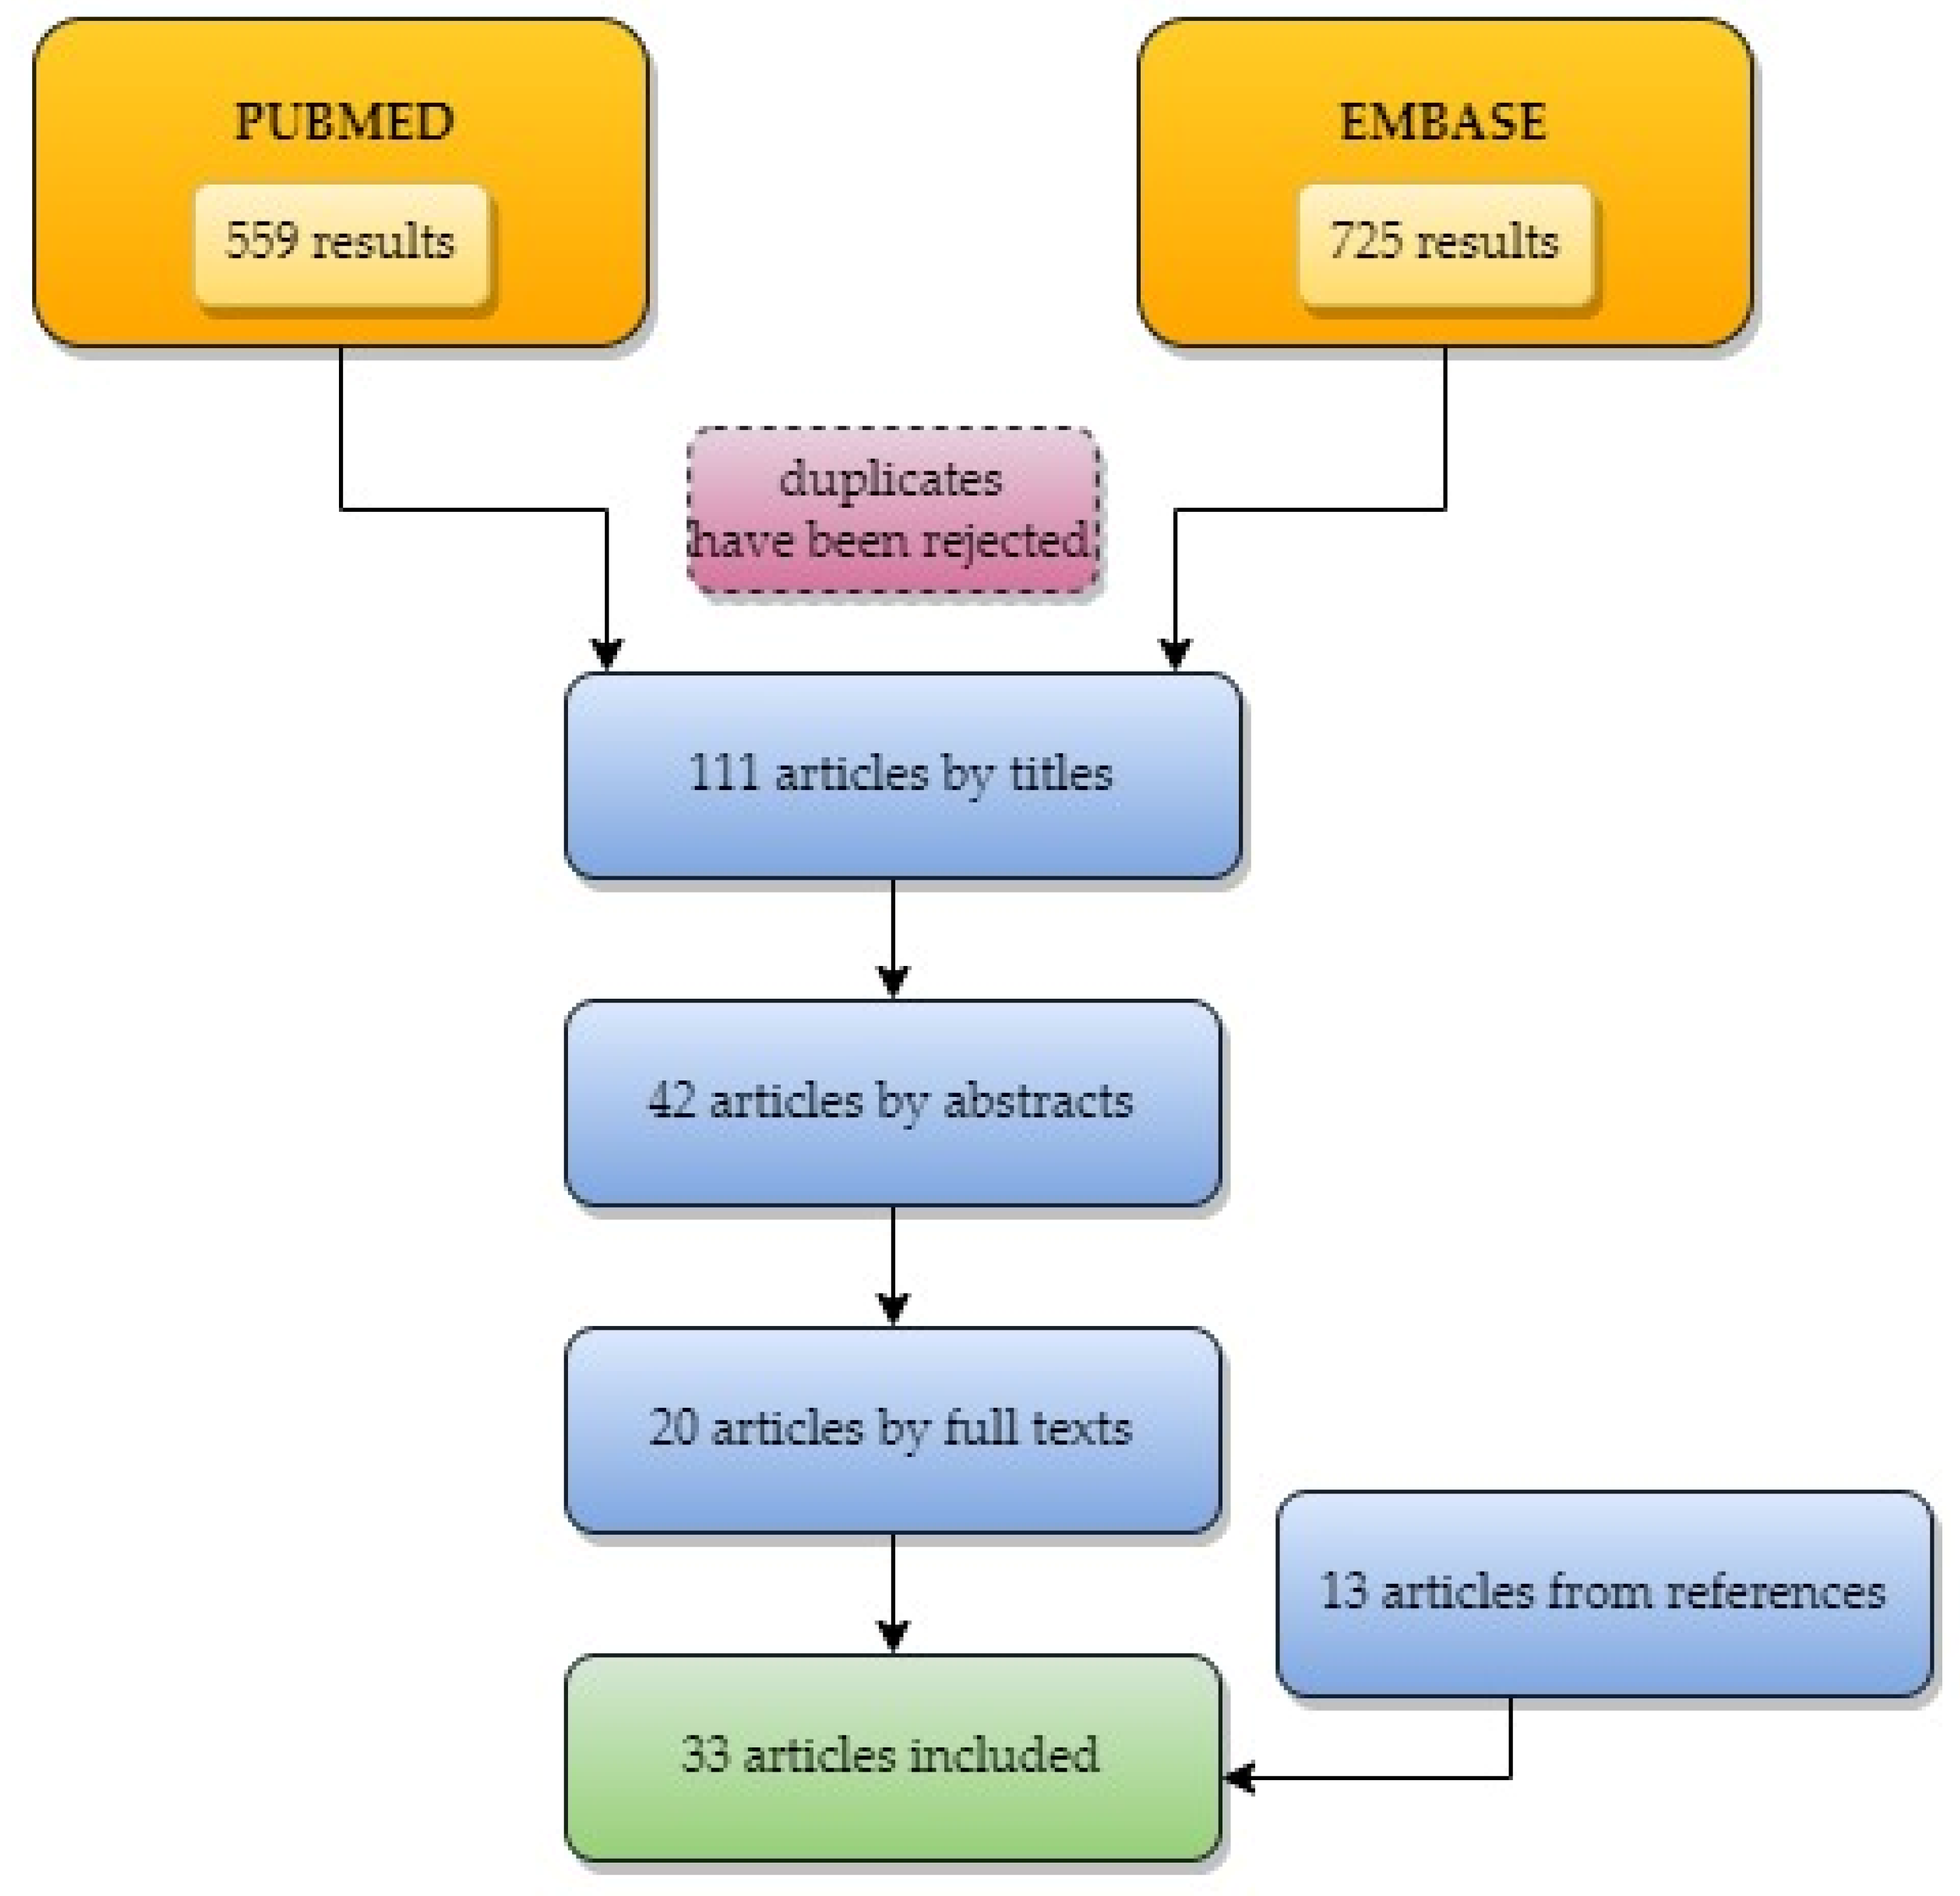
In order to review all studies on the intracystic biomarkers for the differential diagnosis of pancreatic cysts, we searched two publication databases: PubMed and Embase. Combinations of the following keywords were used in queries: “cyst*” AND “pancreatic” AND “pancreas” AND “biomarker*” AND “marker*”. The asterisks allowed us to retrieve records where query words appeared with suffixes (e.g., biomarker|s). The search was limited to publications published between 1 January 2012 and 1 April 2022. No language restrictions were applied, although reports and publications in languages other than English were filtered out in the following curation steps. Duplicate records from the databases were removed before the first eligibility screening was performed. The exclusion criteria were as follows: experimental studies (including animal studies and in vitro research), studies in children, non-original articles, articles on non-biochemical biomarkers (including genetic), studies not on biomarkers, and non-English language articles. Two authors (DW-G and EP) conducted all literature searches. All authors (DW-G, EP, and KN) separately reviewed the titles, the abstracts, as well as the full papers based on the selection criteria, and decided on the suitability of articles for inclusion. All authors then searched the eligible articles. Furthermore, references of the selected papers were cross-searched for omitted relevant articles. Analysis of data was conducted according to PRISMA recommendations. The selection process is presented in Figure 2.
Figure 2.
Flowchart presenting the selection process.
Weighted averages (WA) for two most widely studied markers, CEA and glucose, were calculated using the formula WA = (W1X1 + W2X2 + W3X3 +… + WnXn)/(W1 + W2 + W3 +… + Wn), where w is the number of cases in a single publication and x is the mean for the variable studied.
3. Results
Ultimately, 33 articles were included in the systematic review, of which 20 articles assessed intracystic concentrations of carcinoembryonic antigen, and 11 articles assessed intracystic concentrations of glucose. The remaining markers that were included in the systematic review were evaluated among the total number of 19 articles; however, single markers had literature that did not exceed three papers.
Most of the studies were based on groups of patients that did not exceed 100 people. The tested fluid was collected by EUS or during surgical resection of a pancreatic cystic lesion. Only in one study was fluid withdrawn during endoscopic retrograde cholangiopancreatography (ERCP).
3.1. Interpretative Synthesis of Data: Carcinoembryonic Antigen
CEA is a non-specific marker whose elevated serum concentration is common in neoplastic diseases, typically in colorectal and pancreatic cancer, and is less common in cancers of the stomach, breast, bronchus, lung, or bladder. However, it may be also present in higher concentrations in non-neoplastic diseases such as hepatitis and liver cirrhosis, chronic pancreatitis, gastric and duodenal ulcer disease, inflammatory bowel diseases, and during pregnancy. CEA cannot be used in cancer screening but using it can help assess the efficacy of oncological treatment, recognize local recurrence as well as distant metastases, and for long-term follow-up of patients after cancer treatment [5].
Among the various markers of cystic fluid (collected during EUS or surgical resection of the lesion), CEA is the most extensively studied. CEA has already found its application in distinguishing mucinous from non-mucinous cysts. Furthermore, it is recommended by the guidelines on pancreatic cystic neoplasms, and is the only biomarker that is widely used in clinical practice [4].
There were 20 papers found that related to intracystic CEA (Table 1). The majority of the identified papers on CEA were retrospective studies (n = 13). The numbers of patients included in the studies varied from 17 to 226; however, the majority of papers involved numbers that did not exceed 100 patients. The level of CEA was higher in mucinous cysts than in non-mucinous cysts. The most commonly used cut-off value for the differentiation between mucinous and non-mucinous cysts was 192 ng/mL. The sensitivity at this value ranged from approximately 50 to 75%, with the average being approximately 65%. Few publications took into account other cut-off points; for instance, 317 ng/mL obtained a sensitivity of 89% [6], while for a value of 48 ng/mL, the sensitivity was 72.4% [7]. When referring to the specificity at the cut-off point above 192 ng/mL, it was noted that it ranged from about 80% to 100%, which will most likely distinguish mucinous from non-mucinous lesions. The accuracy ranged from 46% to 84%. WA for CEA was 195 ng/mL.
Table 1.
Intracystic CEA levels in the differentiation of pancreatic cystic lesions.
The combination of CEA with other markers, such as glucose, prostaglandin E-2 (PGE-2), vascular endothelial growth factor A (VEGF-A), and gastricsin, improved the accuracy in distinguishing mucinous from non-mucinous cysts [8,9,10,11,12,13].
As yet, prospective studies involving larger cohorts of patients are necessary, in order to further assess the diagnostic efficacy of such combinations.
3.2. Interpretative Synthesis of Data: Glucose
The second most often-studied intracystic biomarker was glucose, which was reported in 11 papers (Table 2). Blood and serum glucose concentration is a simple, available, and broadly used biomarker; it is used routinely in clinical practice. Glucose measurement is quick, easy to perform, and inexpensive. It can be determined by a laboratory test, with a glucometer, or a strip test. It is a repeatable method that requires only a small amount of cyst fluid [5].
Table 2.
Intracystic glucose levels in differentiating pancreatic cystic lesions.
The majority of the studies had prospective design (n = 6); moreover, the majority of studies (n = 6) were published in 2020 and later. The numbers of patients that were included in the evaluated papers ranged from 17 to 153, and the majority of the studies did not exceed 100 patients. The most common cut-off point for glucose was 50 mg/dL. Concentrations below 50 mg/dL were cited for mucinous cysts, and above 50 mg/dL for non-mucinous cysts, with sensitivities, specificities, and accuracies all above 90% (for non-mucinous cysts: 96%, 93.6%, and 94.6%) [24]. WA for glucose was 44 mg/dL. The diagnostic value at the cut-off point of 66 mg/dL had a sensitivity of 94%, a specificity of only 64%, with an accuracy of 84% [16]. The same study also compared glucose to CEA. CEA at the cut-off point above 192 ng/mL had a sensitivity, specificity, and accuracy of 73%, 89%, and 77%, respectively, which demonstrated the advantage of glucose over CEA in terms of sensitivity, specificity, and accuracy in the differentiation between mucinous and non-mucinous cysts.
In nine papers, both glucose and CEA markers were evaluated. Glucose had a significant advantage in sensitivity, specificity, and accuracy over CEA as well as CA 19-9. Thus, glucose may be considered to be used as a routine diagnostic test for pancreatic mucinous cysts. The glucose test is an inexpensive, simple, and broadly available analysis. Whether measured with a laboratory test, a glucometer, or a reagent strip, its levels were found to be significantly lower in mucinous cysts compared to pancreatic non-mucosal cysts. One of the limitations of glucose as a differentiating marker is that pseudocysts, similarly with mucinous cysts, present low glucose levels; only the addition of a second marker, such as CEA, improved diagnostic efficacy [23].
3.3. Interpretative Synthesis of Data: Other Biomarkers
Our search identified 19 papers related to biochemical intracystic biomarkers other than CEA and glucose that were studied in pancreatic cystic lesions (Table 3).
Table 3.
Other intracystic biomarkers used in differentiating pancreatic cystic lesions.
Among them was cancer antigen 19-9 (CA 19-9). No common cut-off point that could be applied in practical use was found in the analyzed studies. With the cut-off point above 21.395 kU/L, the specificity, sensitivity, and accuracy were 66%, 78%, and 76%, respectively. CA 19-9 levels were higher in mucinous than in non-mucinous cysts [6]. In the study by Talar-Wojnarowska et al. [15], it was concluded that CA 19-9 levels in pancreatic cyst fluid are less specific compared to CEA, especially in the detection of mucinous cysts. A combination analysis involving several markers simultaneously can improve the accuracy of differential diagnosis. Elevated CA 19-9 levels were found in patients with malignant cysts; low CA 19-9 levels (below 37 U/mL) suggested benign lesions [15].
Another marker that may be useful to analyze pancreatic cyst fluid is amylase. The specificity, sensitivity, and accuracy of amylase were assessed at 80%, 54%, and 68% at the cut-off point of 3.073 U/L. Amylase levels were higher in pseudocysts than in mucinous cysts [6]. In the other study, it was found that the highest level of amylase was associated with pseudocysts, especially in patients with a history of acute pancreatitis [15]. Therefore, use of amylase should be limited to confirm the presence of pseudocysts in patients with a history of pancreatitis.
CA 72-4 is also a marker that deserves attention. In a study that involved a group of over 100 patients, it was found that the CA 72-4 level is higher in mucinous cysts than in non-mucinous cysts, with a high sensitivity of the tests at 94%, quite a low specificity of 73%, and an accuracy of 87% [6]. Similar results were obtained in another study that involved a group of approximately 100 patients [22]. In turn, the combination of CA 72-4 with CEA did not improve the sensitivity, specificity, or the accuracy in distinguishing mucinous from non-mucinous cysts compared to using CEA alone [22].
Another biomarker that can bring us closer to the so-called “perfect marker” is VEGF-A, which had 100% sensitivity, a specificity of over 83%, and an accuracy of close to 100% [12]. It also should be noted that VEGF-A was the only marker that is an exact fluid biomarker for SCN [5]. In addition, the combination of CEA with VEGF-A achieved 95.5% sensitivity and 100% specificity, with 99.3% accuracy. Therefore, VEGF-A requires further intensive research.
Due to knowledge gaps concerning the remaining biomarkers, which result mainly from small numbers of studies on small groups of patients, these markers cannot currently be considered for application in clinical practice. Further research regarding these markers is needed.
4. Conclusions
The collection of fluid from the pancreatic cyst in EUS and further biochemical analysis of its composition are very useful in assessing the risk of malignancy, and for making further diagnostic and therapeutic decisions. Despite the progress made in the identification of novel biomarkers in the cystic fluid and supporting the differentiation of the PCLs, their application in clinical practice is still limited to CEA. CEA is the best-tested biomarker thus far; however, it is glucose that has greater sensitivity, specificity, and accuracy in distinguishing mucinous from non-mucinous cysts. Using a combination of the two markers is the most effective. Unfortunately, other biomarkers identified in this systematic review require further research, as data on their diagnostic potential are still limited and they cannot be in widespread use. Therefore, it should be highlighted that the glucose assay, which is available, simple, and inexpensive, could serve as a differentiating marker in clinical practice, despite the mechanisms leading to different glucose levels in different cyst types being unclear. Glucose, due to its diagnostic efficiency and simple measurement, may in the future replace CEA in the differential diagnosis of cysts. However, among the limitations of the existing studies on glucose in PCLs, the different cut-off values applied by the authors must be considered. Most probably, only a combination of several markers may bring us closer to making correct diagnoses. For instance, simultaneous determination of glucose and CEA levels resulted in higher sensitivity.
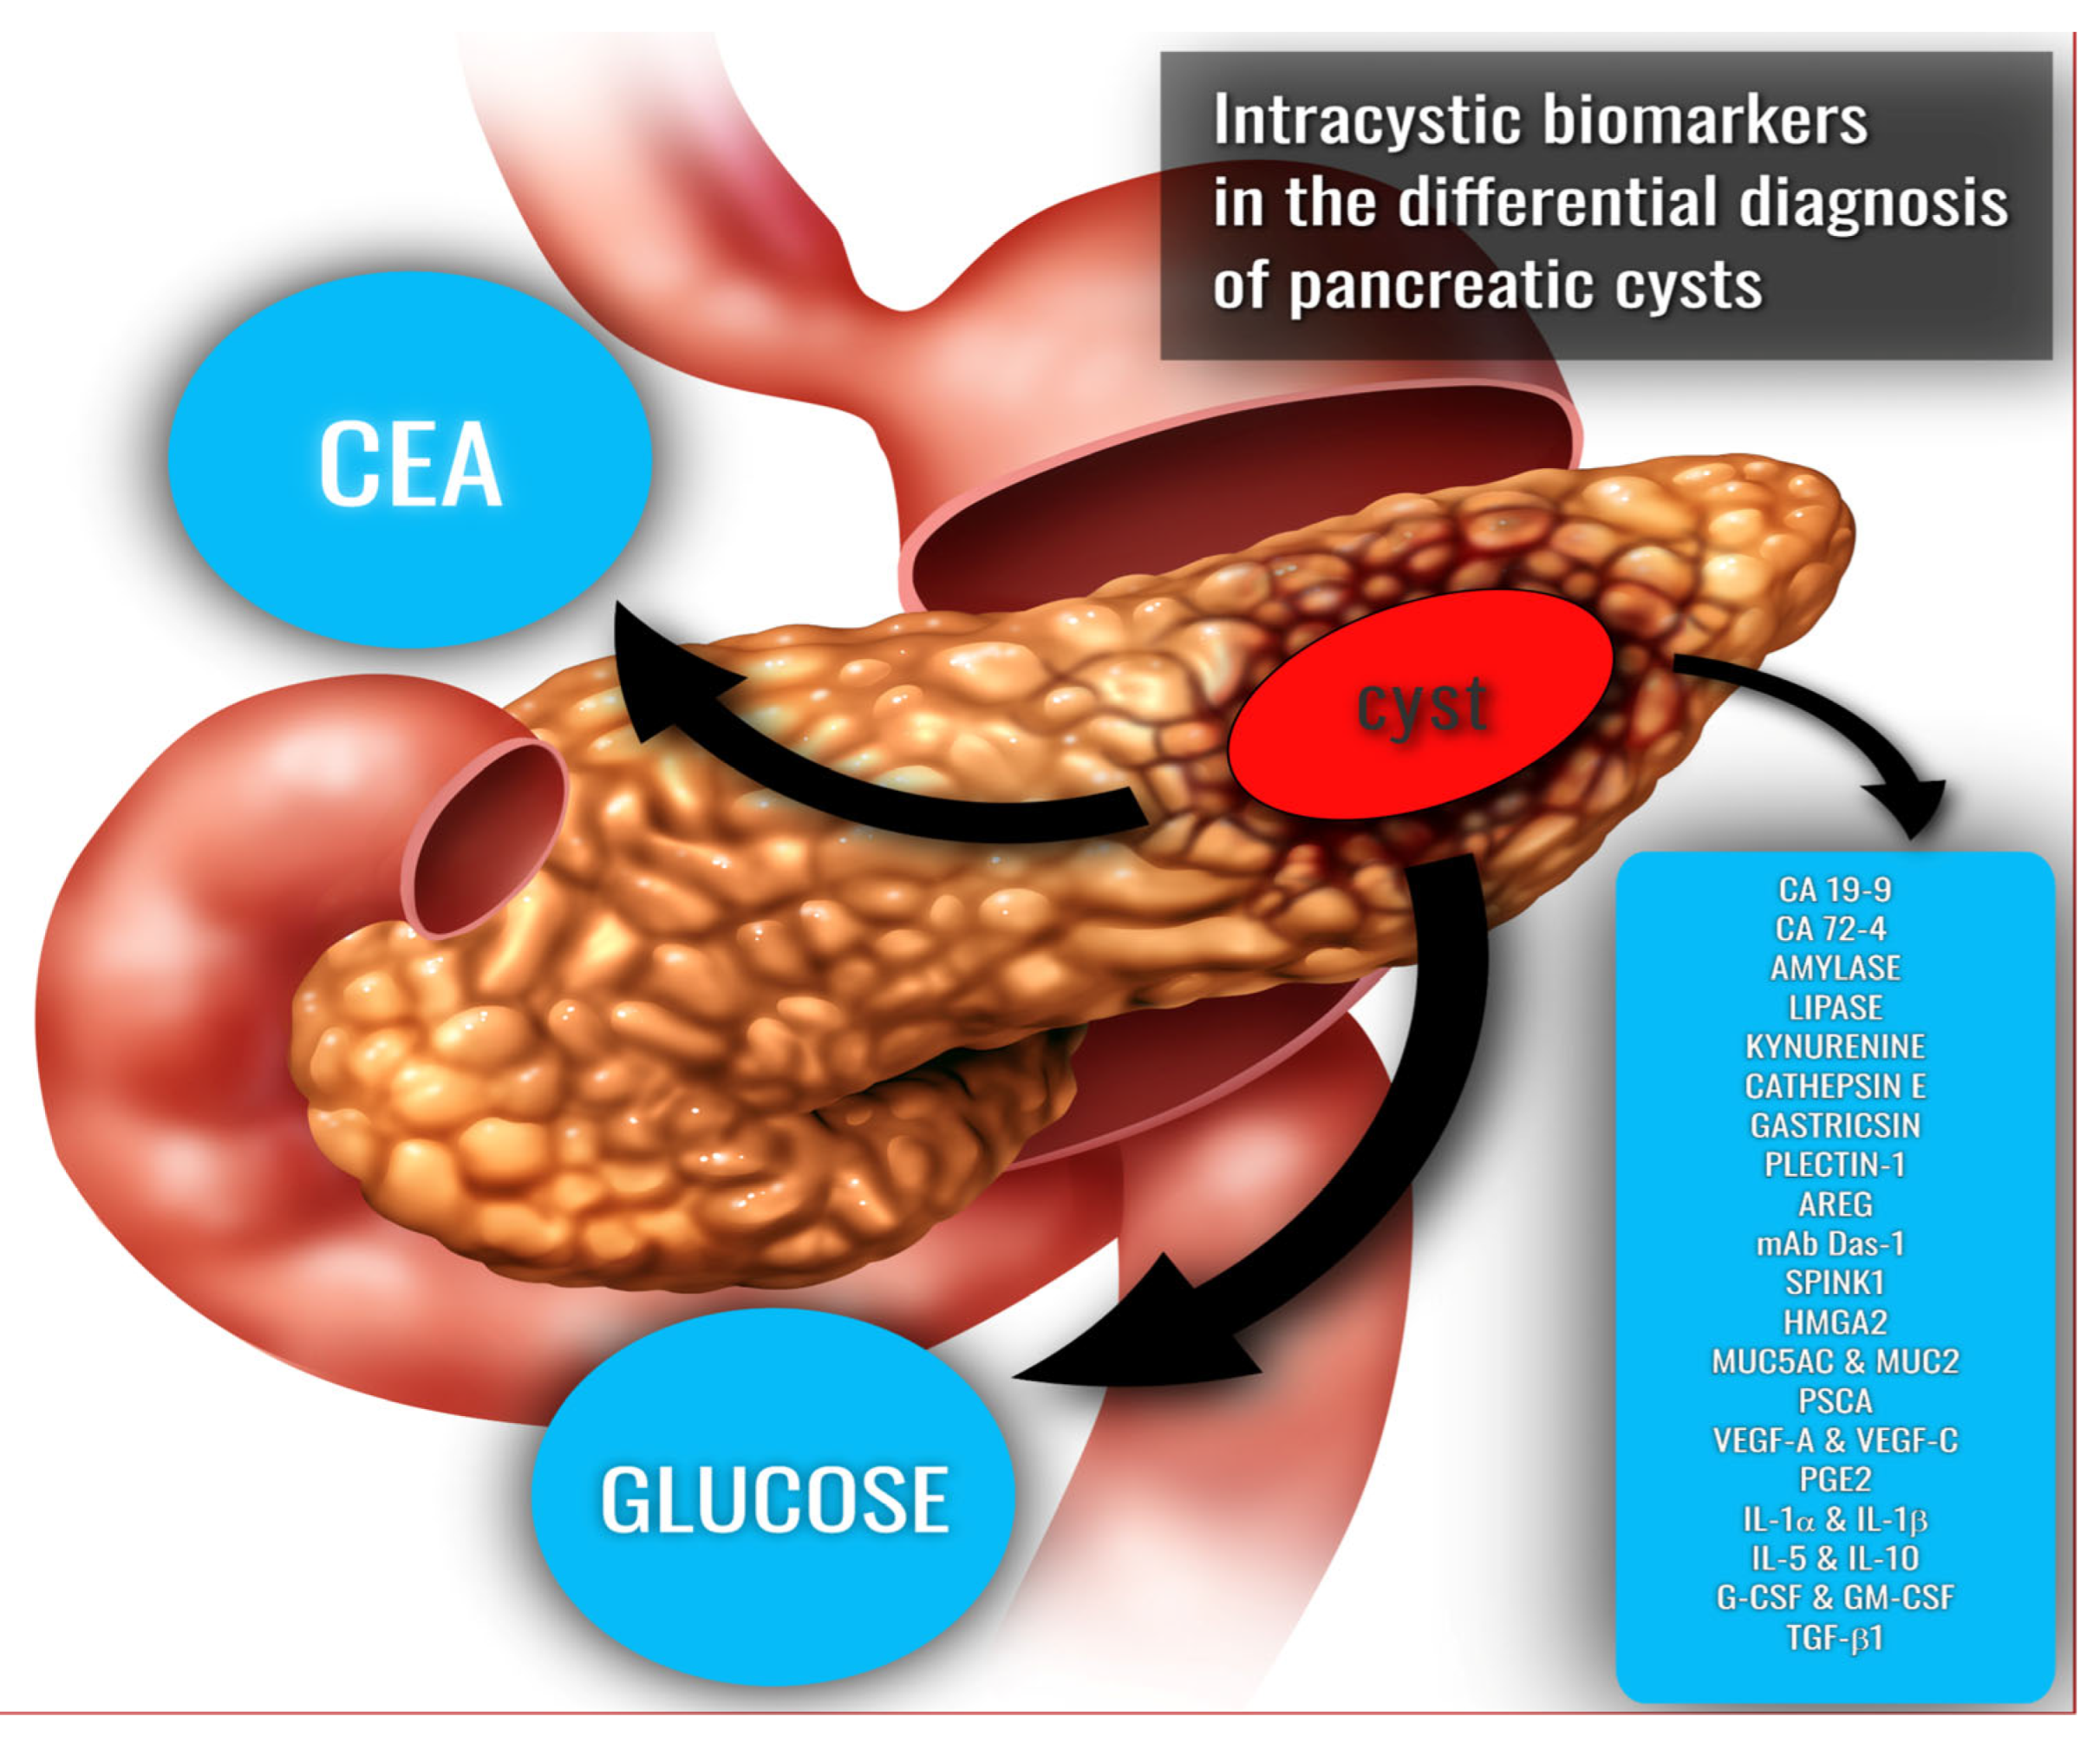
In summary, the perfect biochemical marker that allows for precise classification and risk stratification of pancreatic cystic lesions is still not available, and the existing indices play a supplementary role in the diagnostic process (Figure 3). Considering the growing number of patients with PCLs and their consequences, which involve multiple imaging tests and surgical interventions, further research is needed to find a novel single marker or a panel of markers that would allow health care personnel to clearly define the nature of the examined lesion and exclude its malignancy. This may help save patients from unnecessary surgeries, while qualifying others for appropriate treatment at an early stage of the disease.
Figure 3.
Biochemical intracystic biomarkers in pancreatic cystic lesions. CEA, carcinoembryonic antigen; CA 19-9, cancer antigen 19-9; CA 72-4, cancer antigen 72-4; AREG, amphiregulin; mAb Das-1, monoclonal antibody against a colonic epithelial antigen; SPINK1, serine protease inhibitor Kazal-type 1; HMGA2, high-mobility group AT-hook 2; MUC5AC, mucin 5AC; MUC2, mucin 2; PSCA, prostate stem cell antigen; VEGF-A, vascular endothelial growth factor-A; VEGF-C, vascular endothelial growth factor-C; PGE2, prostaglandin E2; IL-1α, interleukin 1 alpha; IL-1β, interleukin 1 beta; IL-5, interleukin 5; IL-10, interleukin 10; G-CSF, granulocyte colony-stimulating factor; GM-CSF, granulocyte-macrophage colony-stimulating factor; TGF-β1, transforming growth factor β1. An image made by Lightspring/Shutterstock.com was used to create this graphic.
Author Contributions
Conceptualization, D.W.-G. and K.N.; methodology, D.W.-G., E.P. and K.N.; writing—original draft preparation, D.W.-G., E.P. and K.N.; writing—review and editing, D.W.-G., E.P. and K.N.; visualization, D.W.-G. and K.N. All authors have read and agreed to the published version of the manuscript.
Funding
This research received no external funding.
Institutional Review Board Statement
Not applicable.
Informed Consent Statement
Not applicable.
Data Availability Statement
Not applicable.
Conflicts of Interest
The authors declare no conflict of interest.
References
- Mizrahi, J.D.; Surana, R.; Valle, J.W.; Shroff, R.T. Pancreatic Cancer. Lancet 2020, 395, 2008–2020. [Google Scholar] [CrossRef] [Scilit]
- Lanke, G.; Lee, J.H. Similarities and Differences in Guidelines for the Management of Pancreatic Cysts. World J. Gastroenterol. 2020, 26, 1128–1141. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Faias, S.; Pereira, L.; Fonseca, R.; Chaves, P.; Dias Pereira, A.; Cravo, M. A Second Endoscopic Ultrasound with Fine-Needle Aspiration for Cytology Identifies High-Risk Pancreatic Cysts Overlooked by Current Guidelines. Diagn. Cytopathol. 2021, 49, 109–118. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- European Study Group on Cystic Tumours of the Pancreas. European Evidence-Based Guidelines on Pancreatic Cystic Neoplasms. Gut 2018, 67, 789–804. [Google Scholar] [CrossRef] [Scilit]
- Hao, C.; Zhang, G.; Zhang, L. Chapter Eleven—Serum CEA Levels in 49 Different Types of Cancer and Noncancer Diseases. In Glycans and Glycosaminoglycans as Clinical Biomarkers and Therapeutics—Part A; Zhang, L., Ed.; Progress in Molecular Biology and Translational Science; Academic Press: Cambridge, MA, USA, 2019; Volume 162, pp. 213–227. [Google Scholar]
- Levy, A.; Popovici, T.; Bories, D.P.-N. Tumor Markers in Pancreatic Cystic Fluids for Diagnosis of Malignant Cysts. Int. J. Biol. Markers 2017, 32, 291–296. [Google Scholar] [CrossRef] [Scilit]
- Oh, S.H.; Lee, J.K.; Lee, K.T.; Lee, K.H.; Woo, Y.S.; Noh, D.H. The Combination of Cyst Fluid Carcinoembryonic Antigen, Cytology and Viscosity Increases the Diagnostic Accuracy of Mucinous Pancreatic Cysts. Gut Liver 2017, 11, 283–289. [Google Scholar] [CrossRef] [Scilit]
- Yadav, D.; Chahal, P.; Vargo, J.; Sanaka, M.; Jang, S.; Zuccaro, G. Clinical Utility of Intracystic Glucose Levels in Differentiating Mucinous From Non-Mucinous Pancreatic Cysts: 226. Off. J. Am. Coll. Gastroenterol.|ACG 2014, 109, S70. [Google Scholar] [CrossRef] [Scilit]
- Zikos, T.; Pham, K.; Bowen, R.; Chen, A.M.; Banerjee, S.; Friedland, S.; Dua, M.M.; Norton, J.A.; Poultsides, G.A.; Visser, B.C.; et al. Cyst Fluid Glucose Is Rapidly Feasible and Accurate in Diagnosing Mucinous Pancreatic Cysts. Off. J. Am. Coll. Gastroenterol.|ACG 2015, 110, 909–914. [Google Scholar] [CrossRef] [Scilit]
- Simons-Linares, C.R.; Yadav, D.; Lopez, R.; Bhatt, A.; Jang, S.; El-Khider, F.; Sanaka, M.; Stevens, T.; Vargo, J.; Chahal, P. The Utility of Intracystic Glucose Levels in Differentiating Mucinous from Non-Mucinous Pancreatic Cysts. Pancreatology 2020, 20, 1386–1392. [Google Scholar] [CrossRef] [Scilit]
- Yip-Schneider, M.T.; Carr, R.A.; Wu, H.; Schmidt, C.M. Prostaglandin E(2): A Pancreatic Fluid Biomarker of Intraductal Papillary Mucinous Neoplasm Dysplasia. J. Am. Coll. Surg. 2017, 225, 481–487. [Google Scholar] [CrossRef] [Scilit]
- Carr, R.A.; Yip-Schneider, M.T.; Dolejs, S.; Hancock, B.A.; Wu, H.; Radovich, M.; Schmidt, C.M. Pancreatic Cyst Fluid Vascular Endothelial Growth Factor A and Carcinoembryonic Antigen: A Highly Accurate Test for the Diagnosis of Serous Cystic Neoplasm. J. Am. Coll. Surg. 2017, 225, 93–100. [Google Scholar] [CrossRef] [Scilit]
- Ivry, S.L.; Sharib, J.M.; Dominguez, D.A.; Roy, N.; Hatcher, S.E.; Yip-Schneider, M.T.; Schmidt, C.M.; Brand, R.E.; Park, W.G.; Hebrok, M.; et al. Global Protease Activity Profiling Provides Differential Diagnosis of Pancreatic Cysts. Clin. Cancer Res. 2017, 23, 4865–4874. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Kucera, S.; Centeno, B.; Springett, G.; Malafa, M.; Chen, Y.; Weber, J.; Klapman, J. Cyst Fluid Carcinoembryonic Antigen Level Is Not Predictive of Invasive Cancer in Patients with Intraductal Papillary Mucinous Neoplasm of the Pancreas. JOP J. Pancreas 2012, 13, 409–413. [Google Scholar] [CrossRef] [Scilit]
- Talar-Wojnarowska, R.; Pazurek, M.; Durko, L.; Degowska, M.; Rydzewska, G.; Smigielski, J.; Janiak, A.; Olakowski, M.; Lampe, P.; Grzelak, P.; et al. Pancreatic Cyst Fluid Analysis for Differential Diagnosis between Benign and Malignant Lesions. Oncol. Lett. 2013, 5, 613–616. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Park, W.G.; Wu, M.; Bowen, R.; Zheng, M.; Fitch, W.L.; Pai, R.K.; Wodziak, D.; Visser, B.C.; Poultsides, G.A.; Norton, J.A.; et al. Metabolomic-Derived Novel Cyst Fluid Biomarkers for Pancreatic Cysts: Glucose and Kynurenine. Gastrointest. Endosc. 2013, 78, 295–302.e2. [Google Scholar] [CrossRef] [Scilit]
- Nagashio, Y.; Hijioka, S.; Mizuno, N.; Hara, K.; Imaoka, H.; Bhatia, V.; Niwa, Y.; Tajika, M.; Tanaka, T.; Ishihara, M.; et al. Combination of Cyst Fluid CEA and CA 125 Is an Accurate Diagnostic Tool for Differentiating Mucinous Cystic Neoplasms from Intraductal Papillary Mucinous Neoplasms. Pancreatology 2014, 14, 503–509. [Google Scholar] [CrossRef] [Scilit]
- Gaddam, S.; Ge, P.S.; Keach, J.W.; Mullady, D.; Fukami, N.; Edmundowicz, S.A.; Azar, R.R.; Shah, R.J.; Murad, F.M.; Kushnir, V.M.; et al. Suboptimal Accuracy of Carcinoembryonic Antigen in Differentiation of Mucinous and Nonmucinous Pancreatic Cysts: Results of a Large Multicenter Study. Gastrointest. Endosc. 2015, 82, 1060–1069. [Google Scholar] [CrossRef] [Scilit]
- Jin, D.; Small, A.; Vollmer, C.; Jhala, N.; Furth, E.; Ginsberg, G.; Kochman, M.; Ahmad, N.; Chandrasekhara, V. A Lower Cyst Fluid CEA Cut-Off Increases Diagnostic Accuracy in Identifying Mucinous Pancreatic Cystic Lesions. JOP J. Pancreas 2015, 16, 271–277. [Google Scholar] [CrossRef] [Scilit]
- Carr, R.A.; Yip-Schneider, M.T.; Simpson, R.E.; Dolejs, S.; Schneider, J.G.; Wu, H.; Ceppa, E.P.; Park, W.; Schmidt, C.M. Pancreatic Cyst Fluid Glucose: Rapid, Inexpensive, and Accurate Diagnosis of Mucinous Pancreatic Cysts. Surgery 2018, 163, 600–605. [Google Scholar] [CrossRef] [Scilit]
- Jabbar, K.S.; Arike, L.; Verbeke, C.S.; Sadik, R.; Hansson, G.C. Highly Accurate Identification of Cystic Precursor Lesions of Pancreatic Cancer Through Targeted Mass Spectrometry: A Phase IIc Diagnostic Study. J. Clin. Oncol. 2018, 36, 367–375. [Google Scholar] [CrossRef] [Scilit]
- Soyer, O.M.; Baran, B.; Ormeci, A.C.; Sahin, D.; Gokturk, S.; Evirgen, S.; Basar, R.; Firat, P.; Akyuz, F.; Demir, K.; et al. Role of Biochemistry and Cytological Analysis of Cyst Fluid for the Differential Diagnosis of Pancreatic Cysts: A Retrospective Cohort Study. Medicine 2017, 96, e5513. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Faias, S.; Pereira, L.; Roque, R.; Chaves, P.; Torres, J.; Cravo, M.; Pereira, A.D. Excellent Accuracy of Glucose Level in Cystic Fluid for Diagnosis of Pancreatic Mucinous Cysts. Dig. Dis. Sci. 2020, 65, 2071–2078. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Ribaldone, D.G.; Bruno, M.; Gaia, S.; Cantamessa, A.; Bragoni, A.; Caropreso, P.; Sacco, M.; Fagoonee, S.; Saracco, G.M.; De Angelis, C. Differential Diagnosis of Pancreatic Cysts: A Prospective Study on the Role of Intra-Cystic Glucose Concentration. Dig. Liver Dis. 2020, 52, 1026–1032. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Rossi, G.; Petrone, M.; Capurso, G.; Locatelli, M.; Crippa, S.; Doglioni, C.; Mariani, A.; Testoni, S.G.; Archibugi, L.; Tacelli, M.; et al. Sa1421 Glucose Levels in Eus-Aspirated Cyst Fluid Have a High Accuracy for the Diagnosis of Mucinous Pancreatic Cystic Lesions. Gastrointest. Endosc. 2020, 91, AB181. [Google Scholar] [CrossRef] [Scilit]
- Smith, Z.L.; Satyavada, S.; Simons-Linares, R.; Mok, S.R.S.; Martinez Moreno, B.; Aparicio, J.R.; Chahal, P. Intracystic Glucose and Carcinoembryonic Antigen in Differentiating Histologically Confirmed Pancreatic Mucinous Neoplastic Cysts. Off. J. Am. Coll. Gastroenterol.|ACG 2021, 117, 478–485. [Google Scholar] [CrossRef] [Scilit]
- Oria, I.; Lariño-Noia, J.; Villaverde, A.; Pizzala, J.E.; Pasqua, A.; Urgiles, D.; De La Iglesia Garcia, D.; Mejuto, R.; Iglesias-Garcia, J.; Mazza, O.C.; et al. Sa1413 cyst fluid glucose obtained by eus-fna is accurate for the diagnosis of mucinous pancreatic cysts. Experience from two terciary care centers. Gastrointest. Endosc. 2020, 91, AB178–AB179. [Google Scholar] [CrossRef] [Scilit]
- Noia, J.L.; Mejuto, R.; Oria, I.; De la Iglesia-García, D.; Villaverde, A.; Voces, A.; Pizzala, J.; Iglesias-García, J.; Urgiles, D.; Marcolongo, M.; et al. Rapid Diagnosis of Mucinous Cystic Pancreatic Lesions by On-Site Cyst Fluid Glucometry. Surg. Endosc. 2022, 36, 2473–2479. [Google Scholar] [CrossRef] [Scilit]
- Lee, L.S.; Bellizzi, A.M.; Banks, P.A.; Sainani, N.I.; Kadiyala, V.; Suleiman, S.; Conwell, D.L.; Paulo, J.A. Differentiating Branch Duct and Mixed IPMN in Endoscopically Collected Pancreatic Cyst Fluid via Cytokine Analysis. Gastroenterol. Res. Pract. 2012, 2012, 247309. [Google Scholar] [CrossRef] [Scilit]
- Tun, M.T.; Pai, R.K.; Kwok, S.; Dong, A.; Gupta, A.; Visser, B.C.; Norton, J.A.; Poultsides, G.A.; Banerjee, S.; Van Dam, J.; et al. Diagnostic Accuracy of Cyst Fluid Amphiregulin in Pancreatic Cysts. BMC Gastroenterol. 2012, 12, 15. [Google Scholar] [CrossRef] [Scilit]
- Das, K.K.; Xiao, H.; Geng, X.; Fernandez-Del-Castillo, C.; Morales-Oyarvide, V.; Daglilar, E.; Forcione, D.G.; Bounds, B.C.; Brugge, W.R.; Pitman, M.B.; et al. MAb Das-1 Is Specific for High-Risk and Malignant Intraductal Papillary Mucinous Neoplasm (IPMN). Gut 2014, 63, 1626–1634. [Google Scholar] [CrossRef] [Scilit]
- Räty, S.; Sand, J.; Laukkarinen, J.; Vasama, K.; Bassi, C.; Salvia, R.; Nordback, I. Cyst Fluid SPINK1 May Help to Differentiate Benign and Potentially Malignant Cystic Pancreatic Lesions. Pancreatology 2013, 13, 530–533. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Yip-Schneider, M.T.; Wu, H.; Dumas, R.P.; Hancock, B.A.; Agaram, N.; Radovich, M.; Schmidt, M.C. Vascular Endothelial Growth Factor, a Novel and Highly Accurate Pancreatic Fluid Biomarker for Serous Pancreatic Cysts. J. Am. Coll. Surg. 2014, 218, 608–617. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- DiMaio, C.J.; Weis-Garcia, F.; Bagiella, E.; Tang, L.H.; Allen, P.J. Pancreatic Cyst Fluid Concentration of High-Mobility Group A2 Protein Acts as a Differential Biomarker of Dysplasia in Intraductal Papillary Mucinous Neoplasm. Gastrointest. Endosc. 2016, 83, 1205–1209. [Google Scholar] [CrossRef] [Scilit] [PubMed]
- Moris, M.; Dawson, D.W.; Jiang, J.; Lewis, J.; Nassar, A.; Takeuchi, K.K.; Lay, A.R.; Zhai, Q.; Donahue, T.R.; Kelly, K.A.; et al. Plectin-1 as a Biomarker of Malignant Progression in Intraductal Papillary Mucinous Neoplasms: A Multicenter Study. Pancreas 2016, 45, 1353–1358. [Google Scholar] [CrossRef] [Scilit]
- Das, K.K.; Geng, X.; Brown, J.W.; Morales-Oyarvide, V.; Huynh, T.; Pergolini, I.; Pitman, M.B.; Ferrone, C.; Al Efishat, M.; Haviland, D.; et al. Cross Validation of the Monoclonal Antibody Das-1 in Identification of High-Risk Mucinous Pancreatic Cystic Lesions. Gastroenterology 2019, 157, 720–730.e2. [Google Scholar] [CrossRef] [Scilit]
- Simpson, R.E.; Yip-Schneider, M.T.; Flick, K.F.; Wu, H.; Colgate, C.L.; Schmidt, C.M. Pancreatic Fluid Interleukin-1β Complements Prostaglandin E2 and Serum Carbohydrate Antigen 19-9 in Prediction of Intraductal Papillary Mucinous Neoplasm Dysplasia. Pancreas 2019, 48, 1026–1031. [Google Scholar] [CrossRef] [Scilit]
- Siu, L.; Paredes, J.; Kurbatov, V.; Ramachandran, R.; Serafini, F.; Grossman, E.; Gress, F.; Martello, L. Clinical Utility of Cytokine Biomarker Analysis of Pancreatic Cyst Fluid Obtained by Endoscopic Ultrasound Fine Needle Aspiration: A Pilot Study. Pancreas 2019, 48, e60–e61. [Google Scholar] [CrossRef] [Scilit]

Publisher’s Note: MDPI stays neutral with regard to jurisdictional claims in published maps and institutional affiliations. |
© 2022 by the authors. Licensee MDPI, Basel, Switzerland. This article is an open access article distributed under the terms and conditions of the Creative Commons Attribution (CC BY) license (https://creativecommons.org/licenses/by/4.0/).