Skip to Content
You are currently on the new version of our website. Access the old version .
  • 1.0
    Impact Factor
  • 1.9
    CiteScore
  • 19 days
    Submission to First Decision
  • 4 days
    Acceptance to Publication

European Burn Journal

European Burn Journal (formerly European Journal of Burn Care) is an international, peer-reviewed, open access journal on burn care and burn prevention, published quarterly online. It is the official journal of the European Burns Association (EBA).

Get Alerted

Add your email address to receive forthcoming issues of this journal.

All Articles (271)

  • Article
  • Open Access

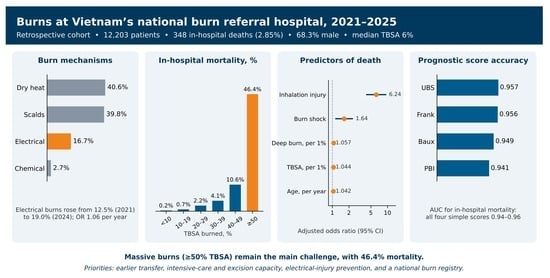
Contemporary longitudinal data on burn epidemiology in Southeast Asia are limited. We conducted a retrospective cohort study of 12,203 patients admitted to Vietnam’s national burn referral hospital from 2021 to 2025. The primary outcome was in-hospital mortality. Factors associated with mortality were assessed using multivariable logistic regression, and the discrimination of the Baux score, Frank index, Unit Burn Score (UBS), and Prognostic Burn Index (PBI) was evaluated using receiver operating characteristic analysis. Overall, 68.3% of patients were male, mean age was 27.8 ± 21.8 years, and median total body surface area (TBSA) burned was 6% (interquartile range 2–14%). Dry heat (40.6%) and scalds (39.8%) predominated. The proportion of electrical burns increased from 12.5% in 2021 to 19.0% in 2024 and 16.0% in 2025 (odds ratio per year 1.064; 95% confidence interval 1.028–1.100). In-hospital mortality was 2.85% (348 deaths), showed no significant temporal trend, and reached 46.4% at TBSA ≥ 50%. Older age, larger TBSA, greater deep-burn extent, inhalation injury, and burn shock were independently associated with death. Areas under the curve were 0.957 (UBS), 0.956 (Frank), 0.949 (Baux), and 0.941 (PBI). These data provide a contemporary benchmark for burn prevention, risk stratification, and service planning in Vietnam.

Eur. Burn J.

12 November 2026

Annual burn admissions and proportion of electrical burns, 2021–2025. Bars show total annual admissions (left axis); the line shows electrical burns as a percentage of annual admissions (right axis).
  • Article
  • Open Access

Background: Sepsis remains a leading cause of late mortality in critically ill burn patients. The optimal hemodynamic strategy, including vasopressor combinations, corticosteroids, and landiolol therapy, remains incompletely defined in this population. Objective: To examine factors associated with landiolol therapy, vasopressor strategies, and corticosteroid use in burn patients with vasopressor-dependent sepsis, and to evaluate their relationship with organ dysfunction and clinical outcomes. Methods: We conducted a preliminary exploratory retrospective cohort study in a specialized burn intensive care unit (ICU) over a three-year period (2022–2024). All mechanically ventilated adult burn patients who developed sepsis requiring vasopressor support during ICU stay were included. The primary exposure of interest was landiolol therapy; five outcomes were assessed for this exposure (ventilator-free days at day 28 after sepsis onset, duration of mechanical ventilation after sepsis onset, ICU length of stay after sepsis onset, acute kidney injury [AKI] after sepsis, and ICU mortality). Hydrocortisone administration and dual vasopressor therapy with norepinephrine plus vasopressin were evaluated as secondary descriptive exposures. Results: Thirty-one patients were included (mean age 55.8 ± 15.3 years; mean TBSA 40.2 ± 13.3%). ICU mortality was 35.5% (11/31). Landiolol was administered in 41.9% of patients; all treated patients were in sinus tachycardia (heart rate 111–140 beats/min), whereas all untreated patients had heart rates <95 beats/min at sepsis onset. No differences were detected for any outcome: ventilator-free days at day 28 (18 [0–23.5] vs. 0 [0–17] days; multiplicity-adjusted p = 0.97), mechanical ventilation duration after sepsis onset (10 [4.5–23] vs. 15 [4.75–53.25] days; multiplicity-adjusted p > 0.99), ICU length of stay after sepsis onset (41 [21–62] vs. 56 [15–106.25] days; multiplicity-adjusted p > 0.99), AKI (2/13 vs. 5/18; OR 0.47, 95% CI 0.08–2.93; multiplicity-adjusted p > 0.99), and ICU mortality (6/13 vs. 5/18; OR 2.23, 95% CI 0.50–10.00; multiplicity-adjusted p > 0.99). The shorter total mechanical ventilation duration in landiolol-treated patients (24 [7–38] vs. 53 [18.75–79.75] days) reflected shorter ventilation before sepsis onset (6 [3–16] vs. 16.5 [10–36.75] days) and the competing risk of early death (six of eleven deaths occurred within 28 days of sepsis onset). Dual vasopressor therapy (25.8%) and hydrocortisone (19.4%) identified phenotypes of greater shock severity. Conclusions: In this small preliminary retrospective cohort, protocolized landiolol therapy in sinus-tachycardic patients was feasible and achieved heart-rate targets, but was not associated with detectable differences in clinical outcomes. These exploratory findings warrant adequately powered prospective studies in this population.

Eur. Burn J.

6 November 2026

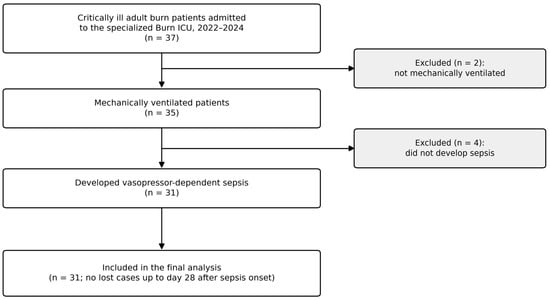
STROBE flow diagram of patient selection. Of 37 critically ill adult burn patients admitted to the specialized Burns ICU during 2022–2024, 2 patients who were not mechanically ventilated and 4 mechanically ventilated patients who did not develop sepsis were excluded; all 31 patients who developed vasopressor-dependent sepsis were included in the analysis.
  • Review
  • Open Access

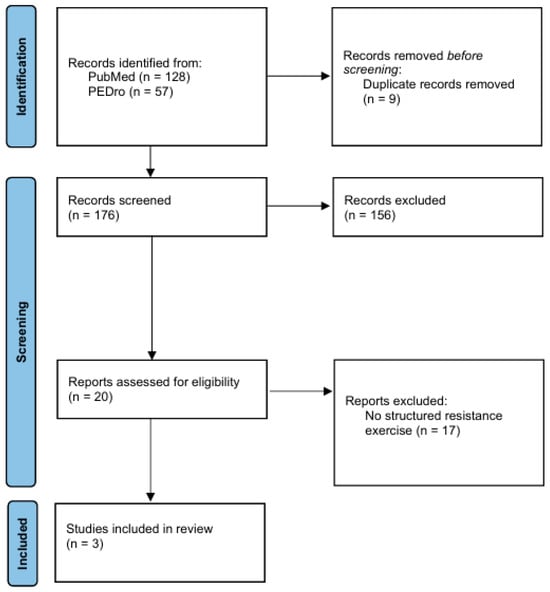
Background: Resistance exercise is a cornerstone of rehabilitation after burn; however prescription of resistance-based exercise during acute adult burn recovery remains empiric and experience-based, varying widely between centres. To understand the contemporary evidence available to guide strength training prescription acutely after burn injury, we conducted a narrative review. Methods: PubMed, PEDro and the supplementary literature were searched for English, Dutch, French and German language human studies evaluating structured resistance training in adult burn populations. Studies eligible for inclusion were: (1) those conducted on humans (no animal or in vitro studies were included); (2) those that investigated the effects of a structured resistance exercise intervention initiated acutely after burn; and (3) those including combined aerobic exercises. The key practical and clinical considerations were timing, dose, monitoring, safety, and outcome selection. Results: After screening, a total of three full-text studies were reviewed. High-quality trials were scarce: three randomised controlled trials implemented structured resistance exercise during the inpatient phase. Study protocols, burn severity, and endpoints were heterogeneous and many functional and quality-of-life outcomes were underpowered. Discussion: There is evidence from multiple independent studies that early, supervised resistance-focused training commenced acutely post-injury is feasible and generally well tolerated, with positive signals for attenuation of muscle wasting and improvements in functional outcomes. Although the evidence base remains limited, the consistency of findings across available studies conducted in different settings and populations increases confidence in these recommendations presented herein. Conclusion: Combining available evidence and reflecting unique, burn-specific constraints, this review presents a revised framework for prescription of resistance training, emphasising individualisation and flexibility and session-by-session progression guided by clinical status and perceived exertion.

Eur. Burn J.

20 October 2026

PRISMA flow diagram of the study identification, screening, and selection process.
  • Feature Paper
  • Article
  • Open Access

Objectives: Microneedling is a promising treatment for hypertrophic scars (HSc); however, documentation of its effects remains limited. The purpose of this study was to objectively quantify scar changes and patient-reported outcomes following microneedling compared with within-patient matched control scars. Methods: Thirty-six adult burn survivors with two similar HSc and who completed the study received five microneedling treatments at six-week intervals in addition to usual care on a randomly assigned HSc. The matched scar received usual care alone. Objective outcomes (elasticity, erythema, melanin, thickness, and transepidermal water loss (TEWL)) were assessed at baseline and at 6 and 12 weeks post-treatment. Participant perception was evaluated using the Patient Scar Assessment Scale at baseline and at 6 weeks post-treatment. Results: Within-scar comparisons at both post-treatment time points demonstrated significant reduction of erythema and TEWL in treated scars and improvement of elasticity and thickness for both scars. Linear mixed-effects models adjusting for baseline values revealed a significant between-group difference favoring the control scar at 6 weeks only for elasticity and the microneedling for erythema and TEWL at 12 weeks. Patient-reported improvements in color, stiffness and thickness were observed for both scars. A significant between-group difference was observed solely for overall scar opinion. Conclusions: Microneedling may enhance specific aspects of scar maturation and improve overall scar opinion.

Eur. Burn J.

19 October 2026

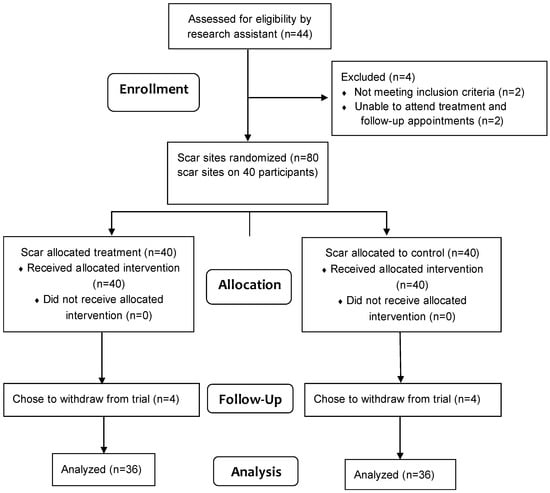
CONSORT flow diagram: Out of the 44 participants assessed for eligibility by the research assistant, 42 were eligible and 40 agreed to participate. Since scars allocated to treatment and control are on the same participant there are two scars per participant so the numbers after allocation are equal.

Highly Accessed Articles

News & Conferences

Latest Issues

Open for Submission

Journal Sections

XFacebookLinkedIn
Eur. Burn J. - ISSN 2673-1991