1. Introduction
The architectural and design layout of a hospital profoundly influences patient healing. The configuration of hospital layouts and facilities may help or hurt the healing process [
1,
2]. Fenestrations are generally recognized as an essential element of architectural design, particularly in hospital architecture, as they can enhance patient rehabilitation by connecting users with nature and outdoor features [
3]. In addition, the impact of natural daylight on the built environment depends on various factors, including the space’s size, shape, atmospheric conditions, materials used, and the distribution of light. These factors collectively influence human peripheral vision, illuminate surroundings, and shape the perception of space [
4]. Moreover, daylighting for hospital rooms must fulfill two main objectives: improving working conditions and promoting a sense of comfort that enhances patient well-being [
5,
6,
7]. Furthermore, a window is a key factor in allowing natural light and providing an external view, which can improve therapeutic outcomes. Nevertheless, windows influence certain environmental characteristics of the indoor environment. Based on its size, position, and shading design, a window affects both visual and thermal comfort, as well as the building’s energy consumption. Therefore, it is essential to optimize window design for optimal performance [
8]. Additionally, fenestrations have been confirmed as an integral component of creating a healing environment, as they provide natural light and visual access to the external world. Multiple studies have demonstrated that access to nature can improve patient outcomes, reduce hospital stays, and minimize the need for pain medication [
9,
10]. Using windows for ventilation may improve indoor air quality and benefit patients. Previous studies have consistently emphasized the significance of natural elements, including vegetation and water features, in the therapeutic environment of healthcare facilities, as they enhance patient outcomes [
11]. Moreover, the rapid modification of healing environment factors has introduced several approaches, one of which concerns the design of inpatient units. The inpatient unit is a vital component of the hospital, providing care for patients who are sick or injured. It offers medication, observation, and various degrees of treatment around the clock, provided by nursing staff. The design of inpatient room windows significantly influences daylighting optimization [
12].
Locally, the healthcare sector in Erbil is experiencing significant growth. Hospitals are a vital part of healthcare services. Furthermore, hospitals in Erbil feature diverse inpatient room designs with various window sizes, shapes, and orientations. While daylight greatly influences human visual functions, it also helps reduce depression, decrease fatigue, and improve alertness. In this context, hospitals serve as architectural phenomena where daylight plays an essential role in patient well-being. This study introduces a novel integrated design framework for inpatient hospital rooms that optimizes daylight performance based on window size, shape, and orientation under Erbil’s specific climatic conditions. Unlike previous research that addresses daylighting in general or in other geographic contexts, this work provides a localized, systematic model that reflects Erbil’s hospital architecture, offering design-based solutions that enhance patient well-being. A hypothetical inpatient room design with multiple orientations demonstrates this, featuring various window sizes and shapes that enhance daylight optimization in Erbil.
2. Literature Review
2.1. Previous Studies on Daylight in Hospitals
Many previous studies have emphasized the importance of daylighting in hospitals. Ref. [
13] illustrated the positive impact of natural lighting on patient health and recovery, as well as its advantages for hospital staff and the hospital environment. Moreover, he examines the physical factors that influence daylighting designs, emphasizing building orientation as a crucial criterion for developing sustainable healthcare environments. He also considers the impact of window design on the psychological and mental well-being of patients and hospital staff, as well as on access to views that facilitate recovery by providing psychological support [
13]. Moreover, Ref. [
14] found that appropriate illumination in the hospital layout enhances the body’s biological cycle, increases transparency and visual clarity, diminishes occupational errors, decreases hospital stays, alleviates pain, reduces depressive feelings, and enhances pleasant emotions [
15] examined the effects of windows on hospital design. The study showed that exposure to natural landscapes reduces post-operative hospital stays by 8%, while daylight exposure enhances serotonin levels, resulting in a 22% reduction in pain perception. The study revealed that prolonged exposure to artificial light in a patient’s room induces psychological and physical issues, including headaches, visual pressure, exhaustion, and depression. Ref. [
16] examine the effects of indoor daylight exposure on psychological stress indicators in hospitals, comparing conditions with sufficient daylight to those with covered windows. Physiological stress was assessed via heart rate variability (HRV) and a survey about participants’ perceptions of their exposure to natural light. In addition, the study by [
17] aims to quantify the relative effectiveness of hospital room windows in terms of energy consumption and natural lighting, examining how key design variables—size, proportion, position, and orientation—impact the primary lighting dynamic metric, Daylight Autonomy (DA). Windows may enhance and complement this feature in holistic healthcare settings. Ref. [
18] examined the impact of daylight exposure on patients in a mental health facility. The study revealed that patients exhibited less nervousness and feelings of depression in environments with greater natural light compared to those with limited light exposure. This illustrates the significance of natural light in promoting well-being and mental health. In addition, research conducted by [
19] revealed that patients with views of the built environment experienced elevated levels of stress, anxiety, and discomfort compared to those with views of nature. The study showed that individuals with a positive view of the external environment typically had shorter hospital stays and incurred lower healthcare costs.
In the same vein, the incorporation of windows for natural ventilation, in addition to the advantages of natural light and views, can improve patient outcomes. Ref. [
20] examined the effects of natural ventilation on patients. The study revealed that patients in rooms with natural ventilation had better breathing ability than those in rooms with mechanical ventilation. Also, it suggests a potential correlation between window design and patient outcomes. Ref. [
21] found that patients with windows facing a park, or other natural views, required less pain medication and had shorter hospital stays [
21]. In addition, the study by [
22] employs a comprehensive approach, combining objective analyses of window characteristics with subjective assessments of patient preferences. The study highlights the significance of holistic design techniques that easily integrate physical features with psychological experiences. Moreover, the study by [
23] has the primary objective of evaluating the optimal window design for bedroom units in intensive care units (ICUs), considering lighting and health parameters. It investigates how window-to-wall ratio (WWR), window position, interior surface reflectance, and room orientation affect visual comfort, lighting performance, energy consumption, and human well-being in ICU spaces.
In sum, many studies have investigated the relationship between daylighting and patient recovery, with supporting evidence. Still, fewer have examined the potential correlation between window design characteristics and daylighting optimization for integrated design models in hospital inpatient rooms.
2.2. Previous Studies on Health Buildings in Erbil City
Numerous studies with diverse objectives have been conducted in the healthcare sector, particularly within hospitals in Erbil City. The study’s primary purpose (is to clarify the correlation between a patient’s health and their physical surroundings, focusing on using natural light as a biophilic strategy in patient rooms in Erbil City [
24]. In the same vein, salutogenic design employs an interdisciplinary approach to study stress reduction and increase coherence, thereby helping people adapt to life’s challenges. The study by [
25] focused on Salutogenic design factors, including daylight and color, in three hospitals. The research utilizes a simulation tool (Ecotect) to calculate daylight in all three hospitals’ wards and lighting distribution (daylight factor) to evaluate the efficiency of Erbil City’s hospital wards. Additionally, the inpatient layout in Erbil City hospitals has been examined for its potential impact on creating a healing environment for users, and the correlation between inpatient typology and healing environments has been investigated [
12]. Regarding the typological analysis, the research conducted by [
26] introduces a Performance-Based Building Design (PBBD) methodology for emergency department (ED) configurations at eight hospitals located in Erbil City. To find out which ED types achieve greater functional aspects. The purpose of the research is to examine three distinct emergency department layout typologies and to evaluate the potential of each to enhance functional efficiency. Eight emergency departments were chosen from eight hospitals in Erbil city. Similarly, the typology of waiting areas in outpatient clinics has been examined for its potential to create a healthy and therapeutic environment for patients and users, particularly in relation to social distancing, and to determine the correlation between outpatient services and the implementation of social distancing in hospitals in Erbil City [
27]. Accordingly, the research conducted by [
28] concentrated on healthcare in Erbil City, examining the satisfaction levels of hospital users (patients or their families) in the lobby area and the application of universal design principles in healthcare facilities.
Figure 1 provides more detail.
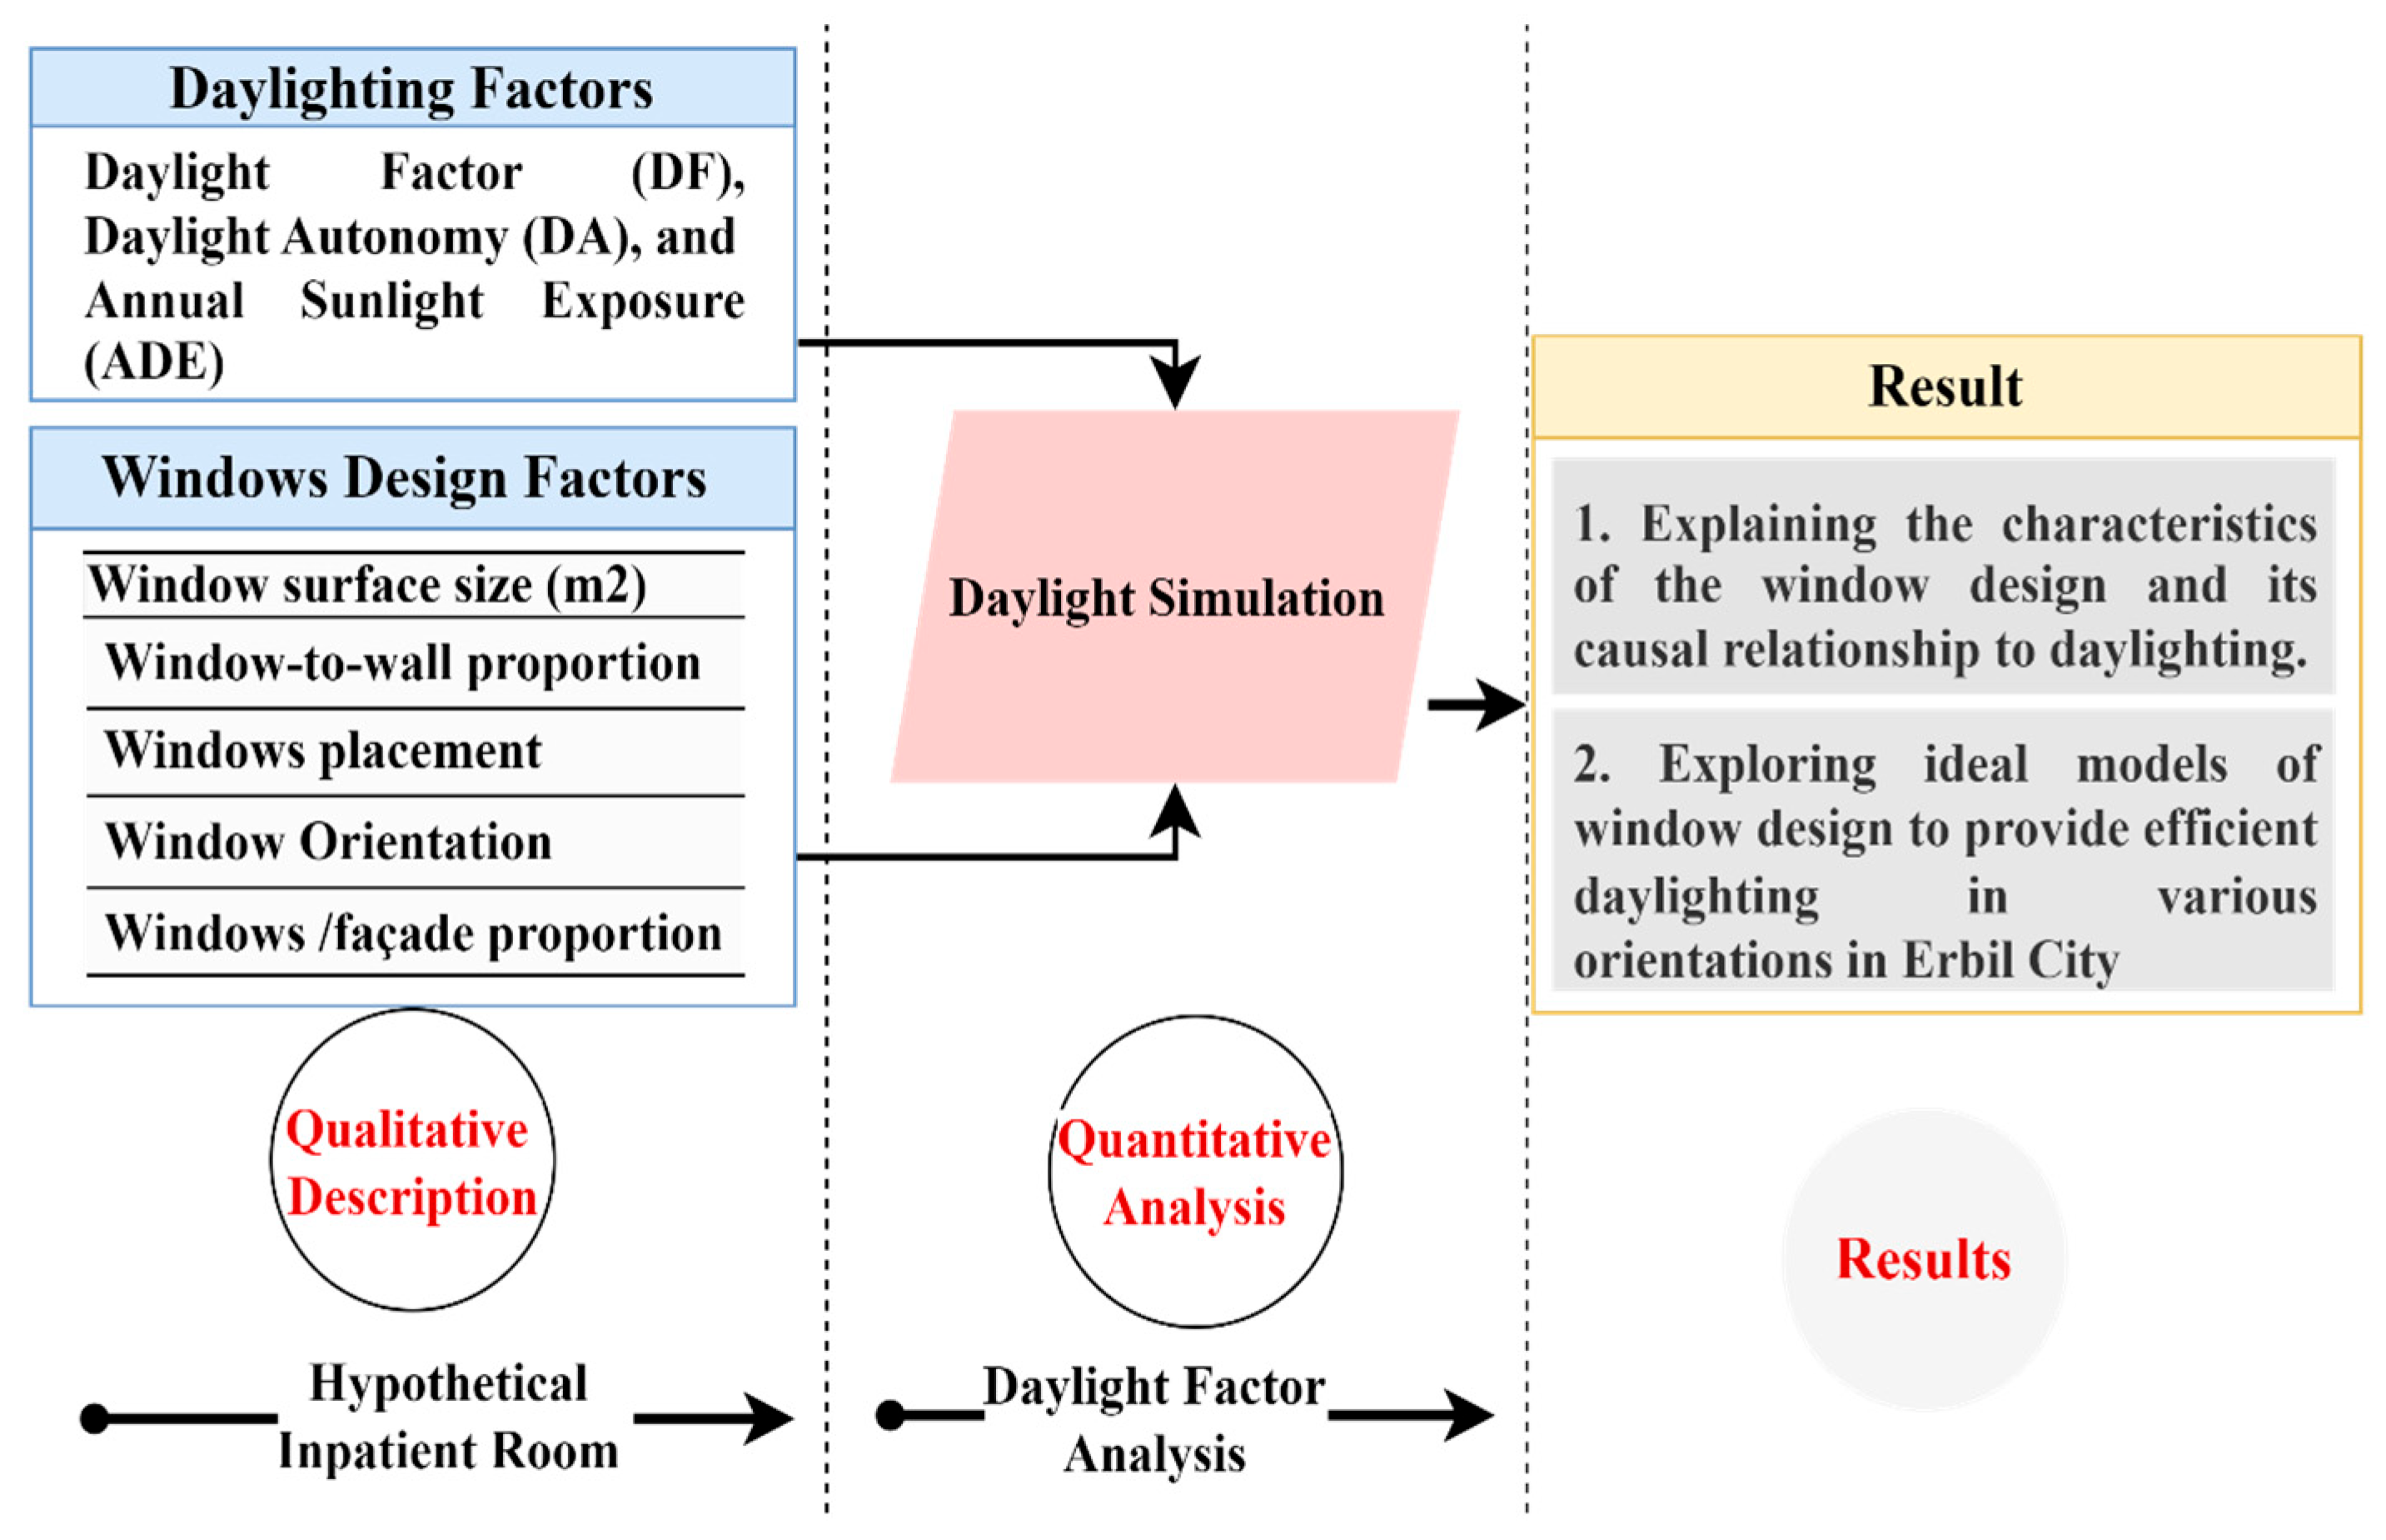
Numerous studies have examined hospital design features, including typological layout analysis, the use of natural light as a biophilic strategy, and the application of universal design principles in hospitals in Erbil City. However, window design features for optimal daylighting in inpatient rooms have not yet been addressed. This study aims to develop integrated design models for hospital inpatient rooms by establishing a framework of window specifications to enhance daylighting for different orientations in Erbil City. This will be done using a mixed-method, qualitative approach to describe window design characteristics. A quantitative approach will be used in the analysis, employing a daylighting simulation tool. Additionally, it investigates the hypothetical layout of inpatient rooms with various orientations to achieve different window designs that optimize daylight in Erbil City.
3. Theoretical Background
3.1. Daylighting in Hospital Buildings
Daylighting design for hospital bedroom spaces must fulfill two primary objectives: optimizing conditions for work performance and creating an environment that enhances patient comfort [
1,
2,
3]. Moreover, it is essential to achieve these objectives while emphasizing the highest achievable level of energy efficiency [
5,
6]. It is important to emphasize how important natural light is since it can reduce the need for electric lighting [
7] while also improving health [
9,
10] and well-being [
13,
14,
15,
16]. Therefore, the decision of a suitable design characteristic value in an inpatient room must be considered during the architectural design process [
14,
15,
16,
17]. Recent developments in computational methods and the introduction of creative, dynamic daylight measurements have led to a new approach to improving window design and luminescence control strategies [
12,
20]. Daylight is the optimal source for enhancing physiological entrainment in humans, as human chrono-regulation has evolved in response to various daylight parameters. Ultimately, daylighting measures, such as DA, align with sustainability objectives and advancing energy-efficient design in healthcare facilities. The International WELL Building Institute has established a standard for healthcare facilities that encompasses aspects of a Healing environment, including access to outdoor spaces, views of nature, and the incorporation of daylight [
29]. Windows are essential for creating a relaxing environment in the architecture of healthcare facilities [
2,
20,
21,
22]. Well-designed windows facilitate natural ventilation, which is necessary for regulating indoor air quality and minimizing the transmission of airborne diseases. Windows allow daylight to enter and provide views of the external environment, both of which have been demonstrated to improve patient outcomes [
22].
Daylighting Parameters
Overall, daylighting has been generally studied by evaluating various characteristics that characterize the connection between human needs and the lighting environment. Numerous studies have examined the essential daylight metrics in this setting. There are four basic metrics: (a) the quantity of daylight, (b) the anticipated glare, (c) the quality of sunshine, and (d) the uniformity of daylight that literature has identified. Among these variable measures, Daylight Autonomy (DA) is notable for its increased accuracy in lighting calculations, since it integrates elements such as orientation, location, and sky types throughout the year [
4,
30,
31]. This statistic evaluates the usage of a specific area based on the annual proportion of hours when daylight alone meets a minimum illuminance threshold. Therefore, employing DA enables the precise adjustment of window placement and dimensions to optimize daylight, thereby reducing reliance on electric illumination during daylight hours. Accordingly, daylight optimization not only markedly decreases energy consumption [
32] but also improves the visual comfort and well-being of humans [
2,
24]. Moreover, the physical quantity is often used to indicate the intensity of light that arrives at a specific location on a surface.
Table 1 highlights the parameters and their recommended values for evaluating daylight quantity, as proposed by previous research and studies.
3.2. Window Design Aspects for Hospital Buildings
Windows served several functions in traditional healthcare buildings. They represented more than simple illumination and ventilation; they also embodied connection and hope. Patients may observe the external environment through a window, which acts as a reminder that life continues [
46]. Numerous cultures saw Windows as gateways between the heavenly and physical world. The psychological component of healing was highlighted in multiple historical healing sites, which featured strategically positioned windows that provided views of gardens and landscapes [
47]. Furthermore, windows in traditional healthcare facilities often reflected the local lifestyle, incorporating elements of art, culture, and religion.
3.2.1. Design Specifications for Inpatient Units
Regarding the design specifications, every patient room must have a minimum of (11.15 m
2) per bed for independent rooms and (9.29 m
2) per bed for double-occupancy rooms, excluding the bathroom and any permanently attached or built-in closets, lockers, or wardrobes [
46]. In addition, every patient room must include a window or a door featuring a clear glass light, with a maximum floor height of (0.914 m), in accordance, the window or door must open directly into an atrium or to the exterior of the building, providing a minimum clear and clear view of 6.10 m, measured parallel from the window or entrance. The minimum net glazed area must be at least 8% of the room’s floor area. Daylight openings in an inpatient room shall be permitted to contain no less than one-tenth of the floor area of the interior room, ranging from 1.86 to 2.23 m
2 [
45,
48].
3.2.2. Effective Windows Parameters for Daylight Optimization
Previously, the dimensions of windows in buildings were primarily influenced by aesthetic factors, neglecting quantitative standards for optimization and energy efficiency [
11,
18]. Several factors have been considered in the design of hospital windows for optimal daylighting. Hence, windows can be created in hospitals to optimize daylighting.
Table 2 provides more details on requirements for Windows design.
4. Research Method
4.1. Research Design
The study’s systematic framework highlights the incorporation of mixed methodologies approaches. Clarify the different types of windows that would be used in the hypothetical hospital inpatient room from a qualitative perspective. Additionally, a daylighting simulation program will be used to quantitatively assess Daylight Factor (DF), Illuminance (ILL), and Daylight Glare Probability (DGP). The proposed research design seeks to accomplish two main objectives:
4.2. Qualitative Approach
Hypothetical Case Study Description: This inpatient room design is created using IES-VE 2024 software and meets key spatial and environmental performance standards based on international guidelines and building codes. The modeled room measures 8700 mm in length and 4000 mm in width, with a total internal area of 34.8 m
2 for a two-bed inpatient layout. A clearance zone of 1200 mm surrounds each bed at the foot and 1430 mm on the sides, allowing for easy movement of patients, staff, and medical equipment. These measurements follow the minimum clearance standards outlined in the International Health Facility Guidelines (IHFG) two-bed layout [
49]. According to the IHFG, each inpatient room must have at least 8% of the floor area as net glazed area, a maximum windowsill height of 914 mm, and an external view extending at least 6.1 m. The model complies with these criteria, featuring a window approximately 2.8 m
2, which exceeds the 8% requirement. The design also adheres to the Florida Building Code (2023), Section 1205.2 [
50], which requires similar natural light access in all habitable rooms, supported by other international standards [
51].
In Iraq, the general building code provides structural and safety provisions but does not include hospital-specific daylighting standards. Therefore, international guidelines were referenced to ensure the model reflects both global best practices and local design realities. Furthermore, previous studies [
52] show that strategic fenestration placement and sizing in the design aim to maximize daylight penetration while minimizing glare and energy use, potentially reducing lighting-related energy consumption by up to 20% in warm climates such as Erbil. The model includes a centrally located window, positioned for optimal daylighting while maintaining patient privacy and comfort.
4.3. Quantitative Approach
4.3.1. Daylight Simulation Procedure
To evaluate daylight performance in the hypothetical inpatient room, daylight simulations were conducted in IES-VE 2024 using the integrated Insight plugin. The simulation setup involved three primary analyses:
- (a)
Daylight Factor (DF) simulation under overcast sky conditions using IES-VE 2024 software’s “Daylight Factor (Beta)” mode.
- (b)
Illuminance Analysis under a clear sky condition at 9:00 AM on 21 September (equinox), to measure daylight illuminance in lux.
- (c)
Daylight Glare probability DGP
Key environmental and simulation parameters included:
Location: Erbil, Iraq (Latitude: 36.19, Longitude: 44.02)
Sky condition data: Global Horizontal Irradiance (GHI: 470 W/m2, DNI: 661 W/m2), Direct Normal Irradiance (DHI: 82 W/m2 at 9 AM).
Illuminance thresholds: The lower bound is set to 100 lux, and the upper bound is at 3000 lux, which aligns with typical comfort and utility benchmarks for patient rooms.
Analysis plane height: Set at 5 inches (~0.127 m) above the floor (IES-VE 2024 software default); results were interpreted to the patient bed level at 0.8 m.
Grid resolution: A 12-inch analysis grid spacing was applied to ensure detailed spatial mapping of light distribution.
A total of 32 window configurations were developed and tested, based on variations in window size, placement, orientation, and proportion. These configurations are detailed in
Section 3.2.2 and
Table 2. Each scenario was simulated under uniform room conditions using IES-VE 2024 and Insight’s daylighting tools to evaluate daylight factor (DF) and illuminance (lux).
4.3.2. Erbil Weather Data
Erbil is located at 36.19° N, 44.02° E, at an altitude of about 420 m above sea level. Its position in the northern subtropics gives it long summer days with high solar angles and shorter winter days with lower sun paths. On the summer solstice (21 June), day length reaches about 14 h 45 min, while on the winter solstice (21 December) it decreases to about 9 h 30 min [
53]. Annual sunshine duration in Erbil exceeds 3200 h, making direct sunlight a dominant daylight source for most of the year. This abundance of daylight presents both opportunities and challenges: while sufficient daylight is generally available, excessive solar penetration in summer months increases the potential for glare and uneven light distribution in patient rooms.
4.3.3. Most Effective Variables for Inpatient Rooms
The daylight performance of the proposed inpatient room was evaluated through simulation and systematically compared to established patient-room daylighting goals (
Table 3). These goals—daylight provision, annual sufficiency, control of direct sunlight, glare prevention, and quality of view—were drawn from international standards and healthcare design guidelines to ensure that the findings extend beyond technical metrics and address patient comfort and well-being.
5. Results and Discussion
5.1. Qualitative Analysis Results
5.1.1. Results of Inpatient Unit Design Specifications
The room layout follows the clearance and dimensional guidelines set by the IHFG, while a 3D Revit model (
Figure 3) was developed to simulate window placement and daylight performance.
Although the model room is hypothetical, its dimensions, clearances, and fenestration ratios were chosen to approximate the range of patient rooms in recently built hospitals in Erbil. International guidelines were followed to ensure compliance with minimum standards while aligning with local practices. A generalized model was used instead of a single case-study ward to create a consistent baseline for comparing multiple fenestration scenarios. This approach ensures both relevance to the Erbil context and reliability of the simulation results.
5.1.2. Window Configuration in the Current Case Study
Although the design adopted in this study is hypothetical, it draws contextual inspiration from existing hospital architecture in Erbil, particularly the typical spatial layout and fenestration strategies. As illustrated in the plan and elevation (
Figure 4 and
Figure 5), real-world hospital designs in Erbil—such as those observed in Rizgary Hospital—typically feature a uniform, single-sided window configuration aligned along the building’s longitudinal façades. In these layouts, patient rooms are arranged in repetitive linear rows, with windows opening to only one side and minimal variation in placement or proportion.
Although this design approach is efficient in terms of construction and cost, it lacks the flexibility and daylighting performance offered by more dynamic fenestration strategies. Consequently, the hypothetical model developed in this study explores alternative configurations—adjusting window size, proportions, orientation, and placement—to assess the potential for daylight improvements in a similar climatic and urban setting.
5.1.3. Window Specification
The current study illustrates multiple options for inpatient room windows, enabling an analysis to determine the most appropriate design for efficient daylighting.
Table 4 provides further details.
The study developed models using the previously described window specifications to illustrate various window characteristics in a matrix correlation (
Figure 6).
Therefore, the characteristics of the window model are summarized in
Table 5.
Alongside the geometric parameters, the windows were defined as clear double-glazed units (6 mm + 12 mm air gap + 6 mm). In the IES-VE material database, these correspond to a solar heat gain coefficient (SHGC) of 0.65 and a visible light transmittance (Tv) of 0.75. These values are consistent with glazing commonly installed in recently constructed hospitals in Erbil, making the simulations representative of local practice.
5.2. Quantitative Analysis Results
The following subsections present results for daylight factor (DF), illuminance distribution, and glare probability (DGP). Each outcome is interpreted in relation to these patient-centered goals to identify which window configurations offer the most supportive daylight environment for hospital wards in Erbil’s hot semi-arid climate.
5.2.1. Glare Analysis Results
The results of the Daylight Glare Probability (DGP) analysis serve as the primary evaluation metric when using the IES-VE software. The results demonstrated generally low DGP values, indicating minimal discomfort glare under diffuse illumination, as shown in
Table 6. More details provided in
Appendix A.
The simulation setup mimicked the patient’s view from bed to evaluate discomfort glare based on realistic eye level and viewing angles. Eight main window configurations were tested under consistent conditions to allow accurate comparisons of glare performance, as shown in
Table 7. Among all the setups, the VDC 20% type (Vertical Decentral at 20% WWR) showed the lowest glare levels, with an average DGP of 11.65, indicating a visually comfortable environment. In contrast, the HCE 30% configuration (Horizontal Central at 30% WWR) records the highest glare levels, averaging 20.57, which suggests a higher risk of discomfort from direct sunlight.
Interestingly, the results confirmed that orientation (SE, SW, NE, and NW) had no significant impact on glare levels. This indicates that, within the room sizes and window proportions used in this study, glare is mainly affected by the window’s shape and placement rather than by which direction the window faces. These results support the idea that when glare reduction is important, design strategies can focus on window layout instead of building orientation.
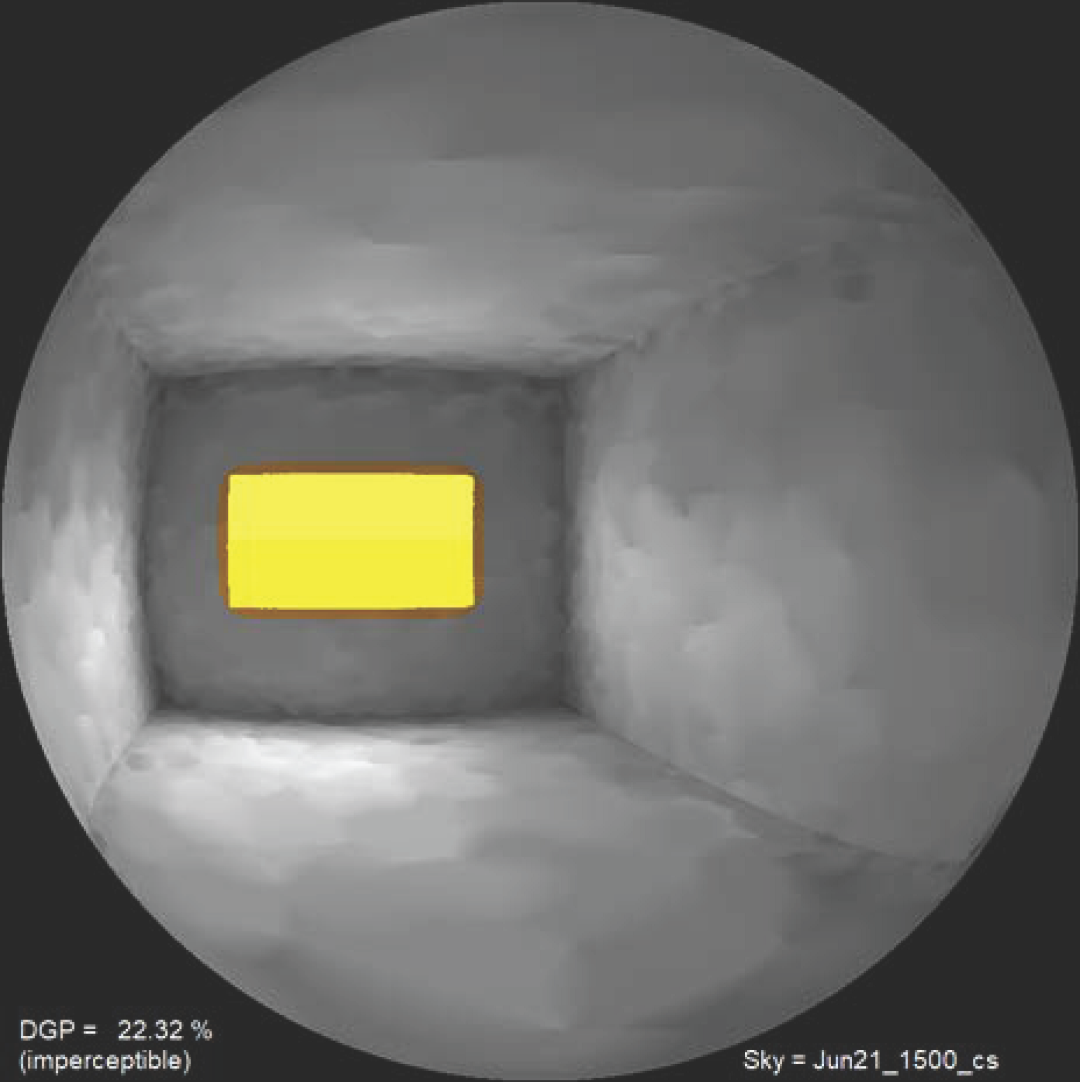
Simulations were performed for three daytime periods (09:00, 12:00, and 15:00) under CIE clear sky conditions on 21 June. June was chosen as the reference period because it represents the peak solar intensity and daylight availability in Erbil’s semi-arid climate, capturing the highest potential for glare discomfort. Representative glare simulation images for each configuration under CIE clear sky conditions are provided in
Appendix B, showing the spatial distribution and intensity of glare across different window types.
5.2.2. Result of Daylight Factor by Orientation
Daylight Factor (DF) analysis across the four orientation-based window models reveals distinct trends in daylight availability (
Table 8).
Appendix B provides more detail.
From
Table 9. The SE 315, SW 45, and NE 225 models showed nearly identical average DF values of 2.5 with minimal variation, demonstrating consistent and adequate daylight performance. Conversely, the NW 135 model recorded a significantly lower average DF of 1.5, proposing insufficient daylighting. While minimum DF values in all models—except NW 135—remained above 0.3, the NW 135 model dropped to 0.0, signaling poor light penetration in some regions of the room.
Maximum DF values were highest in the SE, SW, and NE models (approximately 17.2) and lowest in the NW 135 model (14.1). Furthermore, the percentage of floor area exceeding the 2% DF threshold surpassed 34.9% in the SE, SW, and NE models, but fell sharply to 20.5% in the northwest-oriented room. Measures of daylight uniformity and diversity further reinforce this trend. The NW 135 model exhibited the lowest uniformity (M = 0.0175) and diversity (M = 0.0018), whereas the other three orientations maintained higher values, with uniformity above 0.13 and diversity around 0.02. These findings confirm that the SE, SW, and NE orientations not only deliver higher daylight levels but also provide a more balanced, varied distribution. Contrarily, the NW orientation underperforms across all indicators and may be less suitable for supporting patient comfort and well-being.
6. Discussions
A detailed statistical analysis has been conducted to illustrate the significance of the variables and the effectiveness of the analysis.
6.1. Descriptive and ANOVA Analysis of Daylight Glare Probability (DGP)
The results indicate that west-facing rooms exhibit the highest mean DGP (20.01), suggesting greater glare potential from afternoon sunlight (
Table 10). North-facing rooms show the lowest DGP (18.45), likely due to reduced direct sunlight. The standard deviations indicate moderate variability, with western windows having more consistent glare levels.
The ANOVA results in
Table 11 indicate that orientation does not significantly affect DGP (
p = 0.791), suggesting that, under the tested conditions, the direction of the window has minimal influence on glare.
Higher WWR values lead to increased mean DGP, with 40% WWR producing the highest glare (21.08). Larger windows allow more daylight but also increase the probability of glare.
Table 12 provides more details.
ANOVA results in
Table 13 confirm the significance of WWR on DGP (
p < 0.001). As WWR increases, glare probability also rises, underscoring the need to balance daylight access with glare control in hospital design to ensure visual comfort. This supports the idea that larger windows can improve daylighting but may also lead to discomfort glare.
Table 14 summarizes the DGP values for vertical and horizontal window proportions. Horizontal windows recorded a slightly higher mean DGP (19.93) than vertical ones (18.74), while the standard deviations were similar, indicating comparable variability in glare response.
A one-way ANOVA (
Table 15) showed a significant effect of window proportion on DGP (
p = 0.005), confirming that window configuration influences glare perception. Window proportion significantly affects glare levels. Vertical windows tend to create stronger luminance contrast and localized glare, whereas horizontal windows distribute light more evenly, resulting in better glare control and visual comfort.
Table 16 presents the descriptive statistics of DGP values for central and decentralized window placements. The results indicate that central windows exhibit a higher mean DGP (19.46) than decentralized windows (18.79), implying greater glare potential. The standard deviations are similar, suggesting comparable variability between the two configurations.
The one-way ANOVA revealed a significant effect of window placement on DGP (F = 11.080, p = 0.001), indicating that placement configuration meaningfully influences glare perception. Window placement significantly affects glare performance. Central windows tend to generate stronger luminance contrasts within the visual field, increasing discomfort glare. In contrast, decentralized windows, positioned away from the room’s center, promote a more uniform daylight distribution and consequently lower the probability of glare.
Table 17 presents the descriptive statistics of DGP across three simulation times: morning (09:00), noon (12:00), and afternoon (15:00). The results show that DGP peaks at noon (20.34) due to higher solar intensity, while morning (17.86) and afternoon (19.15) values are comparatively lower.
The one-way ANOVA showed no statistically significant difference in DGP among the three time periods (F = 2.307, p = 0.105). Although midday has the highest average glare values due to peak sunlight, the differences across times are not statistically significant. This indicates that, under the tested clear-sky conditions, the time of day alone does not significantly influence glare probability in patient rooms.
As a summary of glare analysis and effects under CIE Overcast Sky conditions, glare levels in the simulated hospital inpatient rooms remained generally low across all window types, reflecting the diffuse and uniform daylight distribution typical of overcast conditions. This indicates that, under such skies, patients experience minimal visual discomfort regardless of window orientation or size. However, under CIE Clear Sky conditions—more representative of Erbil’s sunny climate, the impact of window design became more pronounced. Larger window-to-wall ratios (WWRs), vertical proportions, and central placements significantly increased the probability of glare, creating higher luminance contrasts in patient views. In contrast, decentralized and horizontally proportioned windows provided more balanced daylight distribution, effectively reducing glare and improving visual comfort for bedridden patients.
Overall, these results highlight that glare in hospital inpatient rooms is mainly influenced by window geometry and placement under clear-sky conditions, while it remains negligible under overcast skies. Designing moderate-sized, horizontally oriented, and decentralized windows can therefore enhance patient visual comfort and well-being by maintaining sufficient daylight without causing discomfort glare.
6.2. Daylight Factor by Orientation
A one-way ANOVA was conducted to assess the impact of window orientation on daylight performance (
Table 18). The analysis revealed statistically significant differences across all six key metrics—Average DF, Minimum, Maximum, % > 2% DF, Uniformity, and Diversity (all F values > 8.1,
p < 0.001). As shown in
Table 18. These results confirm that window orientation has a substantial impact on daylight access and distribution in patient rooms, with northwest-facing configurations performing significantly worse than those in other orientations.
All variables specified statistically significant variation across the four orientations, further highlighting the critical role of window placement in achieving optimal daylighting conditions in hospital patient rooms.
A
t-test analysis was conducted to examine the influence of Window-to-Wall Ratio (WWR) on daylight performance (
Table 19). The results confirm that increasing WWR from 20% to 30% significantly enhances several key lighting metrics. Specifically, average illuminance levels increased from 329.3 lux to 396.2 lux (
p = 0.020), and the percentage of floor area exceeding 500 lux rose from 16.50% to 20.94% (
p = 0.010). Maximum illuminance also showed a statistically significant increase (
p = 0.001). Nonetheless, differences in minimum lux, the percentage of area receiving between 100 and 500 lux, and the area below 100 lux were not statistically significant (
p > 0.05). These findings support the effectiveness of a 30% WWR in enhancing daylight conditions in patient rooms, making it a more suitable option for achieving greater visual comfort in hospital patient room design.
Horizontal window configurations exhibited significantly higher average illuminance compared with vertical ones (406.5 lux vs. 319.1 lux;
p = 0.002), directly indicating enhanced daylight availability within the target performance range. Nevertheless, there was no significant difference in the percentage of floor area within the optimal daylight range of 100–500 lux, which supports visual comfort and functionality (
p = 0.336). While the rate of area above 500 lux was significantly greater in horizontal windows (21.3% vs. 16.1%;
p = 0.002), this increase reflects potential over-illumination rather than optimal performance. Maximum and minimum lux levels did not display statistically significant differences (
p > 0.05). These results validate that while horizontal proportions optimize overall brightness, they do not compromise the distribution of light within the optimal range (100–500 lux). This aligns with observations by [
60,
61], who emphasized the importance of visual access and patient-centered window placement in enhancing perceived comfort and spatial quality. Their study highlights that configuring windows in alignment with the user’s visual field, particularly the foveal and peripheral zones—can contribute to environmental well-being in hospital settings. From a sustainable design perspective, daylight availability mitigates reliance on artificial lighting and supports energy efficiency.
In terms of window placement, only the percentage of floor area exceeding 500 lux showed a statistically significant difference between configurations, with centrally placed windows slightly outperforming those in decentralized locations (20.8% vs. 16.7%;
p = 0.020). However, mean illuminance and area ratio within the 100–500 lux range did not differ significantly (
p > 0.05). This highlights that window placement has less of an impact on achieving critical daylight thresholds than window ratio. These findings align with [
61], who demonstrated that spatial arrangements can affect visibility and wayfinding but allow flexibility in window placement without significantly compromising ambient light quality.
In summary, horizontal windows optimize daylight penetration—particularly in terms of overall brightness—while both horizontal and vertical configurations perform comparably in maintaining comfortable daylight levels. Similarly, although central window placement can marginally increase brightness, both central and decentralized placements provide comparable daylight quality suitable for typical healthcare environments.
Table 20. Provide more details.
The ANOVA results indicated that orientation (F = 33.6,
p < 0.001), WWR (F = 6.8,
p = 0.015), and window proportion (F = 14.5,
p = 0.001) all had statistically significant effects on average illuminance in patient rooms. Conversely, window placement did not have a substantial impact on illuminance levels (F = 1.9,
p = 0.182). Overall, the model accounted for approximately 79.2% of the variance in daylight performance (adjusted R
2 = 0.792), demonstrating strong predictive value. These findings underscore the importance of selecting optimal orientations (SE, SW), adopting larger WWRs (30%), and favoring horizontal proportions to improve natural lighting conditions in healthcare environments.
Table 21 presents the findings of a univariate analysis of variance (ANOVA) evaluating the effects of orientation (model), WWR, window proportion (vertical vs. horizontal), and window placement (central vs. decentralized) on average daylight illuminance levels (lux) in patient rooms.
7. Summary of Findings
Daylight optimization is a fundamental component of patient-centered health-care design. In hospital settings—where patients are often confined to bed for extended periods—access to adequate, well-distributed daylight significantly contributes to psychological well-being, circadian rhythm regulation, and improved recovery outcomes. This research assessed the influence of four key fenestration variables—orientation, WWR, window proportion, and window placement—on daylight performance in inpatient rooms in Erbil City through simulation-based analysis. Performance metrics included Daylight Factor (DF) and average illuminance (lux), with particular attention to the percentage of floor area falling within the recommended range of 100–500 lux.
The findings indicate that orientation has the most decisive influence on daylight factors, with southeast (SE), southwest (SW), and northeast (NE) orientations providing superior daylight access and uniformity. A WWR of 30% produced significantly higher average illuminance (
p = 0.015) while avoiding excessive brightness that could cause glare. Regarding geometry, horizontal window proportions significantly outperformed vertical ones (
p = 0.001), confirming the importance of aspect ratio in enhancing daylight distribution. However, window placement did not have a statistically significant effect on illuminance levels (
p = 0.182), providing greater design flexibility without compromising daylight performance. These insights were synthesized through a summary table that identifies the optimal fenestration strategies based on simulation metrics and statistical validation.
Table 22 provides more details.
As illustrated in this matrix, orientation remains a constraint governed by site conditions; however, the other parameters—WWR, window proportion, and placement—present adaptable design opportunities that can be fine-tuned during the design process. Notably, this research supports an evidence-based strategy to fenestration design, aligning architectural decisions with quantifiable daylighting performance.
These results clearly highlight the importance of passive daylight strategies for both sustainability and health care. They help reduce the need for artificial lighting while improving indoor environmental quality (IEQ). When we design patient rooms with horizontal windows, a balanced window-to-wall ratio, and appropriate orientation, it really enhances visual comfort. Additionally, it plays a significant role in creating a healing environment that prioritizes both performance and patient well-being.
8. Conclusions
Hospitals in Erbil City feature various designs for their inpatient rooms, with windows that come in different sizes, shapes, and orientations. Daylight significantly impacts how well people see, but it also helps reduce their depression and fatigue and improves their alertness. In this way, the hospital is an architectural phenomenon where light plays a crucial role for patients. This work uses orientation, WWR, window proportion, and window placement to maximize daylighting for various orientations in Erbil City, producing integrated design models for hospital inpatient rooms. Developing a hypothetical inpatient room with several orientations and establishing diverse window sizes and shapes maximizes light exposure in Erbil City. To achieve this, a mixed-methods approach was used to qualitatively analyze a hypothetical inpatient room’s Revit 2024 architectural drawing. Sequence used the daylight simulation program (IES-VE 2024 software) to accomplish (DF) and (DGP).
The results indicate that orientation does not influence DF values under overcast skies, as expected. However, it significantly affects illuminance under clear-sky conditions, with southeast (SE), southwest (SW), and northeast (NE) orientations providing higher illuminance and a more uniform distribution than northwest (NW). A window-to-wall ratio of 30% notably increased average illuminance while reducing extreme brightness that could cause glare. Regarding design and geometry, horizontal window proportions greatly exceeded vertical ones, highlighting the importance of aspect ratio in improving daylight dispersion. Window placement had little effect on illumination levels, enabling greater design flexibility without sacrificing daylight performance. The study examined various configurations, including adjustments in window size, proportion, orientation, and location, to explore potential daylighting improvements in a similar urban and climatic setting. Regarding glare performance (DGP), simulations under CIE Overcast Sky conditions showed generally low glare levels, indicating minimal visual discomfort for patients. Under CIE Clear Sky conditions, which represent Erbil’s typical sunny climate, glare varied more significantly. Larger WWRs (40%), vertical window proportions, and central placements increased the likelihood of glare, while horizontal and decentralized configurations lessened it. Combining daylight and glare analyses suggest that the best inpatient-room design includes a 30% WWR, horizontal, decentralized windows, and favorable SE/SW/NE orientations, providing high daylight quality with minimal glare risk.
The study concludes that optimal inpatient-room daylight performance in Erbil’s climate can be achieved with a 30% window-to-wall ratio, horizontal and decentralized window configurations, and SE/SW/NE orientations, which collectively enhance daylight uniformity and reduce glare risk, offering both visual comfort and design flexibility.
Future research should expand on this model by including dynamic daylight metrics, such as Daylight Autonomy (DA) and Daylight Glare Probability (DGP), and by incorporating post-occupancy evaluations or patient feedback to better connect simulation results with real-life experiences.
9. Implications of the Study
The findings of this study provide valuable guidance for designing hospital inpatient rooms in hot, semi-arid climates such as Erbil. Integrating daylight and glare analyses demonstrates that window geometry and placement are critical for achieving visual comfort and energy efficiency. A configuration combining a 30% WWR, horizontal proportion, and decentralized placement offers the best balance between sufficient daylight and minimal glare, particularly under clear-sky conditions typical of Erbil. Such a design improves patient comfort, regulates circadian rhythms, and enhances psychological well-being while reducing visual strain for bedridden occupants. From a sustainability perspective, optimizing daylight performance lessens dependence on artificial lighting and lowers energy consumption. These results emphasize the importance of adopting evidence-based, passive daylighting strategies and incorporating quantitative daylight and glare criteria into hospital design standards to promote both environmental performance and patient-centered healing environments.